


Product Monograph - Stalevo
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Tablets 50/12.5/200 mg, 75/18.75/200 mg, 100/25/200 mg, 125/31.25/200 mg, 150/37.5/200 mg | Croscarmellose sodium, glycerol 85%, hypromellose, magnesium stearate, maize starch, mannitol, polysorbate 80, povidone, red iron oxide (E 172), sucrose, titanium dioxide (E 171), yellow iron oxide (E 172) (note: yellow iron oxide is not used in 75/18.75/200 mg and 125/31.25/200 mg tablets). |
INDICATIONS AND CLINICAL USE
STALEVO® (levodopa, carbidopa and entacapone) is indicated to treat patients with idiopathic Parkinson’s disease:
- To substitute for immediate-release levodopa/carbidopa and entacapone previously administered as individual products.
- To replace immediate-release levodopa/carbidopa therapy (without entacapone) when patients experience the signs and symptoms of end of dose "wearing off" (only recommended when patients are taking a total daily dose of levodopa of 600 mg or less and not experiencing dyskinesias, see DOSAGE AND ADMINISTRATION).
Geriatrics: No adjustment of STALEVO dosage is necessary in elderly patients.
Pediatrics (< 18 years of age): Safety and effectiveness in pediatric patients have not been established. STALEVO is not indicated for use in children under 18 years of age.
CONTRAINDICATIONS
Patients with known hypersensitivity to STALEVO (levodopa, carbidopa and entacapone) or to the excipients of the drug product. For a complete listing, see the
DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
Patients with hepatic impairment (see WARNINGS AND PRECAUTIONS-Hepatic
Impairment).
Co-administration of a non-selective monoamine oxidase (MAO) inhibitors (e.g.
phenelzine and tranylcypromine). The combination of selective MAO-A and selective MAO-B inhibitors is equivalent to non-selective MAO-inhibition, therefore, they should not both be given concomitantly with STALEVO. As with levodopa/carbidopa non-selective MAO inhibitors must be discontinued at least two weeks prior to initiating therapy with STALEVO. Selective MAO-B inhibitors should not be used at higher than recommended doses (e.g. selegiline 10 mg/day) when co-administered with STALEVO (see DRUG INTERACTIONS, Selegiline).
- Patients with clinical or laboratory evidence of uncompensated cardiovascular, endocrine, hematologic, pulmonary (including bronchial asthma), or renal disease.
- Patients with a previous history of Neuroleptic Malignant Syndrome (NMS) and/or non-traumatic rhabdomyolysis.
- As with levodopa, STALEVO should not be given when administration of a sympathomimetic amine is contraindicated.
- Patients with pheochromocytoma due to the increased risk of hypertensive crisis.
- Patients with narrow angle glaucoma.
- Because levodopa may activate a malignant melanoma, STALEVO should not be used in patients with suspicious, undiagnosed skin lesions or a history of melanoma.
WARNINGS AND PRECAUTIONS
Sudden Onset of Sleep
Patients receiving treatment with entacapone in combination with levodopa/dopa decarboxylase (DDC) inhibitor and/or other dopaminergic agents have reported suddenly falling asleep while engaged in activities of daily living, including the driving of a car, which sometimes resulted in accidents. Although some of the patients reported somnolence while treated with levodopa/DDC inhibitor and entacapone, others perceived that they had no warning signs, such as excessive drowsiness, and believed that they were alert immediately prior to the event.
Physicians should alert patients of the reported cases of sudden onset of sleep, bearing in mind that these events are NOT limited to initiation of therapy. Patients should also be advised that sudden onset of sleep has occurred without warning signs and should be specifically asked about
factors that may increase the risk with STALEVO (levodopa, carbidopa and entacapone), such as concomitant medications or the presence of sleep disorders. Given the reported cases of somnolence and sudden onset of sleep (not necessarily preceded by somnolence), physicians should caution patients about the risk of operating hazardous machinery, including driving motor vehicles, while taking STALEVO. If drowsiness or sudden onset of sleep should occur, patients should be informed to refrain from driving or operating machines and to immediately contact their physician.
Episodes of falling asleep while engaged in activities of daily living have also been reported in patients taking other dopaminergic agents, therefore, symptoms may not be alleviated by substituting these products.
While dose reduction clearly reduces the degree of somnolence, there is insufficient information to establish that dose reduction will eliminate episodes of falling asleep while engaged in activities of daily living.
Currently, the precise cause of this event is unknown. It is known that many Parkinson’s disease patients experience alterations in sleep architecture, which results in excessive daytime sleepiness or spontaneous dozing, and that dopaminergic agents can also induce sleepiness.
Skin
Melanoma: Epidemiological studies have shown that patients with Parkinson’s disease have a higher risk (2- to approximately 6-fold higher) of developing melanoma than the general population. Whether the increased risk observed was due to Parkinson’s disease or other factors, such as drugs used to treat Parkinson’s disease, is unclear. For the reasons stated above, patients and healthcare providers are advised to monitor for melanomas frequently and on a regular basis when using STALEVO for any indication. Ideally, periodic skin examinations should be performed by appropriately qualified individuals (e.g., dermatologists).
Prostate Cancer
Prostate cancer has been reported in elderly males during the use of entacapone in combination with levodopa/carbidopa in clinical trials. The clinical relevance of these adverse events is not known (see ADVERSE REACTIONS). Physicians are advised to adhere to the routine examination schedule for all male patients for symptoms and risk factors of prostate cancer, including evaluation prior to initiating treatment with STALEVO. Physicians should emphasize to patients the importance of adhering to routine examinations for prostate cancer during extended treatment with STALEVO (see WARNINGS AND PRECAUTIONS - Information for Patients).
General
STALEVO is not recommended for the treatment of drug-induced extrapyramidal reactions.
Periodic evaluation of hepatic, hematopoietic, cardiovascular and renal function is recommended during extended therapy with STALEVO.
Because carbidopa and entacapone permit more levodopa to reach the brain and more dopamine to be formed, certain dopaminergic adverse effects, e.g. dyskinesias, “on-off” phenomenon, nausea, vomiting and hallucinations may occur at lower doses and earlier with levodopa preparations containing carbidopa and entacapone than with levodopa alone. Therefore, a direct switch from levodopa or levodopa/DDC inhibitor is not recommended for patients who have dyskinesias or whose daily levodopa dose is above 600 mg. In such patients it is recommended that entacapone tablets be introduced as adjunctive therapy to levodopa/DDC inhibitor and the dose of levodopa be adjusted, prior to switching to STALEVO (see DOSAGE AND ADMINISTRATION).
Because STALEVO contains entacapone, it should not be used concurrently with COMTAN® (entacapone). In addition, because STALEVO contains levodopa/DDC inhibitor, the warnings and precautions given for levodopa/DDC inhibitor should be taken into account when STALEVO is used.
If STALEVO treatment is discontinued and the patient is switched to levodopa/DDC inhibitor therapy without entacapone, it is necessary to adjust the dosing of other antiparkinsonian treatments, especially levodopa, to achieve a sufficient level of control of the parkinsonian symptoms (see DOSAGE AND ADMINISTRATION).
Drugs metabolized by Catechol-O-methyltransferase (COMT)
When a single 400 mg dose of entacapone was given together with intravenous isoprenaline (isoproterenol) and epinephrine without coadministered levodopa/DDC inhibitor, the overall mean maximal changes in heart rate during infusion were about 50% and 80% higher than with placebo, for isoprenaline and epinephrine, respectively.
Therefore, drugs known to be metabolized by COMT, such as isoproterenol, epinephrine, norepinephrine, dopamine, dobutamine, alpha-methyldopa, apomorphine, isoetherine and bitolterol should be administered with caution in patients receiving entacapone regardless of the route of administration (including inhalation), as their interaction may result in increased heart rates, possibly arrhythmias, and excessive changes in blood pressure.
Ventricular tachycardia was noted in a 32 year old healthy male volunteer in an interaction study after epinephrine infusion and oral entacapone administration. Treatment with propranolol was required. A causal relationship to entacapone administration appears probable but cannot be attributed with certainty.
Cardiovascular
Myocardial infarction and other ischemic heart disease events have been reported with the use of entacapone in combination with levodopa/DDC inhibitor in clinical trials (see ADVERSE REACTIONS). STALEVO should be administered with caution to patients with ischemic heart
disease or risk factors for cardiovascular disease.
In patients with a history of myocardial infarction or who have residual atrial nodal, or ventricular arrhythmias, cardiac function should be monitored with particular care during the period of initial dosage adjustments in a facility with provisions for intensive cardiac care.
Periodic evaluation of cardiovascular function is recommended during extended therapy with STALEVO.
Orthostatic Hypotension/Syncope
Entacapone may aggravate levodopa-induced orthostatic hypotension. STALEVO should be given with caution to patients who are treated with drugs which may cause orthostatic hypotension. In controlled clinical trials approximately 1.2% of patients who received 200 mg entacapone and 0.8% of patients treated with placebo as adjunct to levodopa/DDC inhibitor reported at least one episode of syncope. Reports of syncope were generally more frequent in patients in both treatment groups who had an episode of documented hypotension.
Endocrine and Metabolism
Patients with fructose intolerance
STALEVO tablets contain sucrose. Therefore, patients with rare hereditary problems of fructose intolerance, glucose-galactose malabsorption or sucrase-isomaltase insufficiency should not take this medicine.
Hormone levels
Of the ingredients in STALEVO, levodopa is known to depress prolactin secretion and increase growth hormone levels.
Gastrointestinal
As with levodopa, treatment with STALEVO may increase the possibility of upper gastrointestinal hemorrhage in patients with a history of peptic ulcer. STALEVO should be administered with caution to these patients.
Since levodopa competes with certain amino acids, the absorption of levodopa may be impaired in some patients on a high protein diet. Excessive acidity also delays stomach emptying, thus delaying absorption of levodopa.
Diarrhea
In clinical trials, diarrhea was reported as an adverse event in 60 of 603 (10.0%) and 16 of 400 (4.0%) of patients treated with 200 mg of entacapone or placebo as adjunct to levodopa/DDC inhibitor, respectively. In patients treated with entacapone, diarrhea was generally mild to moderate in severity (8.6%) but was reported as severe in 1.3%. Diarrhea resulted in withdrawal in 10 of 603 (1.7%) patients (1.2% with mild to moderate diarrhea and 0.3% with severe
diarrhea). Diarrhea generally resolved after discontinuation of entacapone. Two patients with diarrhea required hospitalization. Typically, diarrhea presents within 4 to 12 weeks after entacapone is started, but it may appear as early as the first week and as late as many months after the initiation of treatment. For patients experiencing diarrhea, close monitoring of weight is recommended in order to assess the need for treatment discontinuation to avoid excessive weight loss (see also WARNINGS AND PRECAUTIONS-Hepatic/Biliary/Pancreatic-Abnormal Weight Decrease).
Colitis
Some patients who experienced diarrhea and weight loss during entacapone treatment were subsequently diagnosed with colitis, following colonoscopy and biopsy. Prolonged or persistent diarrhea suspected to be related to STALEVO may be a sign of colitis. In the event of prolonged or persistent diarrhea, the drug should be discontinued and appropriate medical therapy and investigations considered.
Hepatic/Biliary/Pancreatic
Abnormal Weight Decrease
In isolated cases, combined progressive anorexia, asthenia and weight decrease within a relatively short period of time have been reported prior to elevations in liver enzymes and serious hepatic adverse events. For patients who experience progressive anorexia, asthenia and weight decrease within a relatively short period of time, a general medical evaluation including assessment of liver function should be considered (see WARNINGS AND PRECAUTIONS-Gastrointestinal-Diarrhea).
Hepatic Impairment
The metabolism of entacapone is slowed in patients with mild to moderate (Child-Pugh grading Class A and B) hepatic impairment caused by cirrhotic disease. In these patients, the AUC and Cmax values were approximately two-fold greater than those in demographically-matched healthy volunteers. As there are no clinical trial data to establish a safe and effective dosing regimen for hepatically impaired patients, STALEVO should be not be administered to patients with hepatic impairment (see CONTRAINDICATIONS).
Biliary Excretion
Caution should be exercised when administering STALEVO to patients with biliary obstruction, as entacapone is excreted mostly via the bile (see DRUG INTERACTIONS-Drugs interfering with biliary excretion).
Musculoskeletal
Rhabdomyolysis
Rhabdomyolysis secondary to severe dyskinesias or Neuroleptic Malignant Syndrome (NMS) has been observed rarely in patients with Parkinson’s disease. Very rare cases of rhabdomyolysis
have been reported with entacapone treatment.
Symptoms associated with rhabdomyolysis can include muscle pain, muscle tenderness and weakness, bruising, elevated temperature, urinary retention, confusion, and elevated CPK. Acute renal failure is serious complication associated rhabdomyolysis and has been reported in some cases of rhabdomyolysis that have occurred during entacapone treatment.
Neurologic
STALEVO should be used cautiously in patients who have a history of seizures or have conditions associated with seizure or have a lowered seizure threshold.
Neuroleptic Malignant Syndrome
A symptom complex resembling the neuroleptic malignant syndrome (NMS), characterized by elevated temperature, muscular rigidity, altered consciousness (e.g., agitation, confusion, coma), autonomic instability (tachycardia, labile blood pressure) and elevated CPK has been reported in association with the rapid dose reduction, or withdrawal of, or changes in antiparkinsonian therapy, including levodopa/carbidopa and entacapone. In individual cases, only some of these symptoms and/or findings may be evident. This, uncommon but life-threatening, syndrome should be considered in the differential diagnosis for any patient who develops a high fever or severe rigidity.
Cases with similar signs and symptoms have been reported in association with entacapone therapy, especially following abrupt reduction or discontinuation of entacapone and other dopaminergic medications. The complicated nature of these cases makes it difficult to determine what role, if any, entacapone may have played in their pathogenesis. No cases have been reported following abrupt withdrawal or dose reduction of entacapone treatment during clinical studies.
Prescribers should exercise caution when discontinuing STALEVO. If a decision is made to discontinue treatment with STALEVO, withdrawal should proceed slowly. The patient should be monitored closely for signs and/or symptoms and other dopaminergic treatments should be adjusted as needed. If signs and/or symptoms occur despite a slow withdrawal of STALEVO, an increase in levodopa dosage may be necessary. Tapering discontinuation of STALEVO has not been systematically evaluated.
Dyskinesia
Entacapone may potentiate the dopaminergic side effects of levodopa and may cause and/or exacerbate pre-existing dyskinesia. Although decreasing the dose of levodopa may ameliorate this side effect, many patients in controlled trials who received entacapone or placebo as adjunct to levodopa/DDC inhibitor therapy continued to experience frequent dyskinesias despite a reduction in their dose of levodopa. The rates of withdrawal for dyskinesia were 1.5% and 0.8% for 200 mg entacapone and placebo, respectively.
Occupational Hazards: Psychomotor Performance
Entacapone together with levodopa may cause dizziness and symptomatic orthostatism. Therefore, patients should be cautioned about operating machinery, including automobiles, until they are reasonably certain that the drug treatment does not affect them adversely.
STALEVO may have a major influence on the ability to drive and use machines. Patients being treated with STALEVO and presenting with somnolence and/or sudden sleep onset episodes must be instructed to refrain from driving or engaging in activities where impaired alertness may put themselves or others at risk of serious injury or death (e.g. operating machines) until such recurrent episodes have resolved (see WARNINGS AND PRECAUTIONS-Sudden Onset of Sleep).
Ophthalmologic
Patients with chronic wide-angle glaucoma may be treated cautiously with STALEVO provided the intraocular pressure is well controlled and the patient is monitored carefully for changes in intraocular pressure during therapy.
Peri-Operative Considerations
If general anesthesia is required, therapy with STALEVO may be continued for as long as the patient is permitted to take fluids and medication by mouth. If therapy has to be stopped temporarily, STALEVO may be restarted as soon as oral medication can be taken at the same daily dosage as before (see DRUG INTERACTIONS).
Psychiatric
As with levodopa, STALEVO may cause mental disturbances. All patients treated with STALEVO should be monitored carefully for the development of mental changes (e.g. hallucinations and psychoses), depression with suicidal tendencies, and serious antisocial behavior. Patients with past or current psychosis should be treated with caution.
Dopamine Dysregulation Syndrome
Patients and caregivers should be advised to adhere to dosage instructions given by the physician. Patients should be regularly monitored for the development of impulse control disorders. Patients and caregivers should be made aware that behavioral symptoms of impulse control disorders including pathological gambling, increased libido, hypersexuality, compulsive spending or buying, binge eating and compulsive eating can occur in patients treated with dopamine agonists and/or other dopaminergic treatments such as entacapone in association with levodopa. Safety data from various sources including literature, clinical trials, and post-market analysis have described an addictive pattern of dopamine replacement therapy known as dopamine dysregulation syndrome, in which patients use doses in excess of those required to control their motor symptoms. Because patients may not recognize these behaviors as abnormal, it is important for physicians to specifically ask patients and caregivers to identify new behavior patterns. Review of treatment is recommended if such symptoms develop. These symptoms were
generally reversible upon dose reduction or treatment discontinuation (see Post-Market Adverse Drug Reactions, Dopamine Dysregulation Syndrome).
Hallucinations
Dopaminergic therapy in Parkinson’s disease patients has been associated with hallucinations. In clinical trials, hallucinations developed in approximately 4% of patients treated with 200 mg entacapone or placebo, as adjunct to levodopa/dopadacrboxylase inhibitor. Hallucinations led to drug discontinuation and premature withdrawal from clinical trials in 0.8% and 0% of patients treated with 200 mg entacapone and placebo, respectively. Hallucinations led to hospitalization in 1.0% and 0.3% of patients in the 200 mg entacapone and placebo groups, respectively.
Renal
Renal Impairment
The pharmacokinetics of entacapone were not significantly changed in patients with moderate to severe renal impairment. STALEVO should be administered with caution to patients with severe renal disease (see PHARMACOKINETICS, Special Population and Conditions). There is no experience with entacapone in patients receiving dialysis.
Urine, Sweat and Saliva Discoloration
STALEVO may cause a harmless intensification in the color of the patient’s urine to brownish-orange. STALEVO may also cause darkening of sweat and saliva.
Respiratory
Fibrotic Complications
Cases of retroperitoneal fibrosis, pulmonary infiltrates, pleural effusion, and pleural thickening have been reported in some patients treated with ergot derived dopaminergic agents. These complications may resolve when the drug is discontinued, but complete resolution does not always occur. Although these adverse events are believed to be related to the ergoline structure of these compounds, it is unknown whether other, non-ergot derived drugs (e.g., entacapone, levodopa) that increase dopaminergic activity can cause them. It should be noted that the expected incidence of fibrotic complications is so low that even if entacapone caused these complications at rates similar to those attributable to other dopaminergic therapies, it is unlikely that it would have been detected in a cohort of the size exposed to entacapone. Four cases of pulmonary fibrosis were reported during clinical development of entacapone; three of these patients were also treated with pergolide and one with bromocriptine. The duration of treatment with entacapone ranged from 7 to 17 months.
Special Populations
Pregnant Women: There are no studies or clinical experience of the use of STALEVO in pregnant women. Use of STALEVO in women of child-bearing potential requires that the anticipated benefits of the drug be weighed against possible hazards to mother and child.
It has been reported from individual cases that levodopa crosses the human placental barrier, enters the fetus, and is metabolized. Carbidopa concentrations in fetal tissue appeared to be minimal.
Although the effects on human pregnancy are unknown, both levodopa and combinations of carbidopa and levodopa have caused visceral and skeletal malformations in rabbits. Regarding reproduction toxicity of entacapone, decreased fetal weight and a slightly delayed bone development were noticed in rabbits treated at systemic exposure levels in the therapeutic range (see TOXICOLOGY, Teratogenicity).
Nursing Women: Levodopa is excreted in human breast milk. There is evidence that lactation is suppressed during treatment with levodopa. Carbidopa and entacapone were excreted in milk in animals but it is not known whether they are excreted in human breast milk. The safety of levodopa, carbidopa or entacapone in the infant is not known. Women should not breast-feed during treatment with STALEVO.
Pediatrics: The safety and efficacy of STALEVO in children aged below18 years have not been established. STALEVO is not indicated for use in patients below the age of 18.
Geriatrics: No adjustment of STALEVO dosage is necessary in elderly patients.
Concurrent Diseases: STALEVO is contraindicated for patients with clinical or laboratory evidence of uncompensated cardiovascular, endocrine, hematologic, pulmonary (including bronchial asthma), hepatic or renal disease (see CONTRAINDICATIONS).
STALEVO should be administer with caution to patients with ischemic heart disease, biliary obstruction, or history of peptic ulcer disease or convulsions.
Information for Patients
The following information should be discussed by physicians with patients and their caregivers:
- 1. Sudden Onset of Sleep
Physicians should alert patients that cases of sudden onset of sleep have been reported with entacapone in combination with levodopa/DDC inhibitor and/or other dopaminergic agents, and inform them that these events are NOT limited to initiation of therapy. Patients should also be advised that sudden onset of sleep has occurred without warning signs and should be specifically asked about factors that may increase the risk with STALEVO, such as concomitant medications or the presence of sleep disorders. Given the reported cases of somnolence and sudden onset of sleep (not necessarily preceded by somnolence), physicians should caution patients about the risk of operating hazardous machinery, including driving motor vehicles, while taking STALEVO. Patients should be advised to refrain from driving or operating machines and to immediately contact their physician if they experience drowsiness or sudden onset of sleep.
- 2. Monitoring for melanomas
Patients should be advised that studies of people with Parkinson’s disease show that they may be at an increased risk of developing melanoma, when compared to people without Parkinson’s disease. It is not known if this problem is associated with Parkinson’s disease or the drugs used to treat Parkinson’s disease. Therefore, patients and healthcare providers are advised to perform periodic skin examinations when using STALEVO.
- 3. Monitoring for prostate cancer
Patients should be informed that in a study of patients with early stage Parkinson’s disease, who were treated with levodopa/carbidopa or STALEVO for an average of about 3 years, prostate cancer was reported more frequently in the group of patients that received STALEVO. It is not known if treatment with STALEVO affects the risk of having prostate cancer. Therefore, physicians should emphasize to patients the importance of adhering to routine examinations for prostate cancer during extended treatment with STALEVO.
- 4. Prolonged or persistent diarrhea
Patients should be informed that diarrhea may occur with STALEVO and may have a delayed onset. Sometimes prolonged diarrhea has been associated with colitis (inflammation of the large intestine). Should transient, mild diarrhea occur, the patient should drink fluids and monitor for weight loss. If diarrhea persists, without any known cause, patient evaluation by a physician is recommended. If prolonged/persistent diarrhea is suspected to be related to STALEVO, the drug should be discontinued. In case the prolonged diarrhea is due to STALEVO, it seems to resolve usually within few days after stopping the drug. If the cause of prolonged diarrhea remains unclear or continues after stopping entacapone, then further diagnostic investigations should be considered.
- 5. Compulsive behaviors
Patients should be advised that intense urges to gamble, increased sexual urges, other intense urges such as excessive eating or spending, and the inability to control these urges have been reported while taking one or more of the medications that increase central dopaminergic tone, which are generally used for the treatment of Parkinson’s disease, including STALEVO. Prescribers should ask patients about the development of new or increased urges or cravings and should advise patients to report such new urges while being treated with STALEVO. Because these urges have been reported to stop in some cases after dose reduction or stopping medication, physicians should consider these adjustments if a patient develops such urges while taking STALEVO.
Monitoring and Laboratory Tests
The laboratory tests required during extended levodopa therapy should normally be conducted during STALEVO treatment also.
Commonly, levels of blood urea nitrogen, creatinine, and uric acid are lower during
administration of levodopa/carbidopa than with levodopa alone. Transient abnormalities include elevated values of blood urea, AST (SGOT), ALT (SGPT), LDH, bilirubin, and alkaline phosphatase.
Decreased hemoglobin, hematocrit, elevated serum glucose and white blood cells, bacteria and blood in the urine have been reported during levodopa/carbidopa treatment.
Positive Coombs' tests have been reported, both for levodopa/carbidopa and for levodopa alone, but hemolytic anemia is extremely rare.
Levodopa/carbidopa may cause a false positive result when a dipstick is used to test for urinary ketone; this reaction is not altered by boiling the urine sample. The use of glucose oxidase methods may give false negative results for glycosuria.
Entacapone is a chelator of iron. The impact of entacapone on the body’s iron stores is unknown; however, a tendency towards decreased serum iron concentrations was noted in a clinical trial. In a controlled clinical study serum ferritin levels (as marker of iron deficiency and subclinical anemia) were not changed with entacapone compared to placebo after one year of treatment and there was no difference in the rates of anemia or decreased hemoglobin levels.
Cases of falsely diagnosed pheochromocytoma in patients on levodopa/carbidopa therapy have been reported very rarely. Caution should be exercised when interpreting plasma and urine levels of catecholamines and their metabolites in patients on levodopa or levodopa/carbidopa therapy.
Carcinogenesis and Mutagenesis
See TOXICOLOGY - Carcinogenecity studies and Mutagenecity studies
ADVERSE REACTIONS
The following section describes the undesirable effects reported for levodopa/carbidopa and for entacapone used in combination with levodopa/DDC inhibitor.
Adverse Drug Reaction Overview- Levodopa/carbidopa
The most common serious adverse reactions occurring with levodopa/carbidopa are dyskinesias, including choreiform, dystonic and other involuntary movements, and nausea.
Other serious adverse reactions are mental changes including paranoid ideation and psychotic episodes, depression with or without development of suicidal tendencies, and dementia. Convulsions also have occurred; however, a causal relationship with levodopa/carbidopa therapy has not been established.
Other adverse reactions that have been reported with levodopa alone and with various levodopa-carbidopa formulations, and may occur with STALEVO (levodopa, carbidopa and entacapone) are:
Body as a whole: chest pain, asthenia, fatigue.
Cardiovascular: Cardiac irregularities and/or palpitation, syncope, hypotension, orthostatic effects including hypotensive episodes, hypertension, phlebitis, myocardial infarction, irregular heart rhythm.
Gastrointestinal: Vomiting, anorexia, development of duodenal ulcer, diarrhea, dark saliva, constipation, dyspepsia, dry mouth, taste alterations, sialorrhea, dysphagia, bruxism, hiccups, abdominal pain and distress, flatulence, burning sensation of tongue, gastrointestinal pain, heart burn, gastrointestinal hemorrhage.
Hematologic: Leukopenia, hemolytic and non-hemolytic anemia, thrombocytopenia, agranulocytosis.
Hypersensitivity: Angioedema, urticaria, pruritus, Henoch-Schönlein purpura, bullous lesions (including pemphigus-like reactions).
Metabolic: Weight gain or loss, edema
Musculoskeletal: Back pain, shoulder pain, muscle cramps, leg pain.
Nervous System/Psychiatric: Neuroleptic malignant syndrome, (see WARNINGS and PRECAUTIONS), bradykinetic episodes (“on-off” phenomenon), dizziness, somnolence including very rarely excessive daytime somnolence and sudden sleep onset episodes, paresthesia, psychotic episodes including delusions, hallucinations and paranoid ideation, dream abnormalities including nightmares, insomnia, headache, depression with or without development of suicidal tendencies, agitation, confusion, increased libido including hypersexuality, dopamine dysregulation syndrome, decreased mental acuity, disorientation, ataxia, numbness, increased hand tremor, muscle twitching, blepharospasm (which may be taken as an early sign of excess dosage, consideration of dosage reduction may be made at this time), trismus, activation of latent Horner’s syndrome, anxiety, euphoria, falling and gait abnormalities, extrapyramidal disorder, nervousness, mental impairment (e.g. memory impairment, dementia), peripheral neuropathy, psychosis. Convulsions have also occurred, but a causal relationship with levodopa/carbidopa has not been established.
Respiratory: Dyspnea, upper respiratory tract infection, pharyngeal pain, cough.
Skin: Alopecia, rash, dark sweat, flushing, malignant melanoma (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS), hyperhidrosis.
Special Senses: Diplopia, blurred vision, dilated pupils, and oculogyric crises.
Urogenital: Dark urine, urinary frequency, urinary tract infection, urinary retention, urinary incontinence, priapism.
Miscellaneous: Faintness, hoarseness, malaise, hot flashes, sense of stimulation, bizarre
breathing patterns, peripheral edema.
Abnormal Hematologic and Clinical Chemistry Findings
Decreased hemoglobin and hematocrit; abnormalities in alkaline phosphatase, SGOT (AST), SGPT (ALT), lactic dehydrogenase, bilirubin, blood urea nitrogen (BUN), Coombs’ test; elevated serum glucose; white blood cells, bacteria, and blood in the urine, decreased white blood cell count and serum potassium; increased serum creatinine and uric acid; protein and glucose in urine.
Adverse Drug Reaction Overview- Entacapone
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
A total of 1450 patients with Parkinson’s disease received entacapone during the pre-marketing clinical trials. Patients treated in double-blind placebo controlled trials received entacapone or placebo as adjunct to levodopa/DDC inhibitor. Approximately 14% of the 603 patients given entacapone in the double-blind placebo-controlled trials discontinued treatment due to adverse events compared to 9% of the 400 patients who received placebo. The most frequent causes of discontinuation in decreasing order for entacapone vs placebo are: psychiatric reasons (2% vs 1%), diarrhea (2 % vs 0%), dyskinesia/hyperkinesia (2% vs 1%), nausea (2% vs 1%), abdominal pain (1% vs 0%), and aggravation of Parkinson’s disease symptoms (1% vs 1%).
Incidence of Adverse Events in Placebo Controlled Trials
The most frequently observed adverse events reported with entacapone were dyskinesias/hyperkinesia (25%/10%), nausea (14%), abnormal urine (intensification of the color of urine, 10%), diarrhea (10%), dizziness (8%) and abdominal pain (8%). Dyskinesia, nausea and abdominal pain, may be more common with higher doses (> 1,400 mg/day) than with lower doses of entacapone.
Adverse events related to the treatment with entacapone are usually mild to moderate in severity, leading only rarely to discontinuation of the treatment.
Table 1: Adverse events, irrespective of causal relationship to study drug, occurring in > 1% of entacapone patients and > placebo during controlled Phase 3 studies.
| Adverse Events by body system | Entacapone + Levodopa/DDC inhibitor N=603 % of patients | Placebo + Levodopa/DDC inhibitor N=400 % of patients |
Autonomic Nervous System Disorders Hypotension postural | 4.3 | 4.0 |
Body As A Whole - General Disorders Fatigue | 6.1 | 3.5 |
Pain Back pain Sweating increased Asthenia Weight decrease | 6.0 5.0 3.6 1.8 1.7 | 4.5 3.0 3.0 1.3 0.5 |
Fever Syncope | 1.3 1.0 | 0.5 0.8 |
Central & Peripheral Nervous System Disorders Dyskinesia Hyperkinesia Hypokinesia Dizziness Ataxia Speech disorder | 25.2 9.5 8.6 7.5 1.2 1.2 | 14.8 5.0 7.5 6.0 0.5 0.8 |
Gastrointestinal System Disorders Nausea Diarrhea Abdominal pain Constipation Vomiting Mouth dry Dyspepsia Flatulence | 13.8 10.0 8.1 6.3 4.0 3.0 2.3 1.5 | 7.5 4.0 4.5 4.3 1.0 0.3 0.8 0.3 |
| Adverse Events by body system | Entacapone + Levodopa/DDC inhibitor N=603 % of patients | Placebo + Levodopa/DDC inhibitor N=400 % of patients |
Anorexia Gastrointestinal disorders Gastritis | 1.5 1.0 1.0 | 1.3 0.3 0.3 |
Musculoskeletal System Disorders Arthralgia | 1.8 | 1.5 |
Platelet, Bleeding & Clotting Disorders Purpura | 1.5 | 0.8 |
Psychiatric Disorders Hallucinations Nightmares Anxiety | 4.1 2.2 2.0 | 4.0 1.8 1.3 |
Agitation Confusion Somnolence Amnesia Sleep disorder | 1.7 1.7 1.7 1.3 1.3 | 0.3 1.5 0.3 0.8 0.8 |
Reproductive Disorders, Male Prostatic disorder | 1.0 | 0.3 |
Resistance Mechanism Disorders Infection bacterial | 1.3 | 0.0 |
Respiratory System Disorders Dyspnoea Bronchitis | 2.7 1.2 | 1.3 1.0 |
Secondary Terms - Events Fall | 4.1 | 3.5 |
Skin And Appendages Disorders Rash | 3.6 | 3.0 |
| Special Senses Other, Disorders | ||
| Taste perversion | 1.0 | 0.3 |
| Adverse Events by body system | Entacapone + Levodopa/DDC inhibitor N=603 % of patients | Placebo + Levodopa/DDC inhibitor N=400 % of patients |
Urinary System Disorders Urine abnormal Cystitis | 9.5 1.2 | 0.0 0.5 |
Additional adverse events that are not included in the above table but that have been identified as common adverse events associated with the use of entacapone in clinical trials and post-market spontaneous reports include insomnia, parkinsonism aggravated, dystonia, muscle, musculoskeletal and connective tissue pain and chromaturia.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Body As A Whole - General Disorders: malaise, hot flushes, temperature changed sensation, aspiration, oedema generalised, carpal tunnel syndrome, leg pain;
Cardiovascular Disorders, General: hypertension, heart valve disorders;
Central & Peripheral Nervous System Disorders: hypoaesthesia, muscle contractions involuntary, eye abnormality, hypotonia; impulse control disorders (obsessive-compulsive disorder, hypersexuality, akathisia, compulsive lip biting, gambling, libido increased, obsessive thoughts, pathological gambling, sexual activity increased);
Endocrine Disorders: hyperthyroidism;
Gastrointestinal System Disorders: gastroenteritis, oesophagitis, tooth disorder, saliva increased, dysphagia, feces discolored, diverticulitis, change in bowel habits, fecal abnormality;
Heart Rate And Rhythm Disorders: extrasystoles, bradycardia, bundle branch block, fibrillation atrial;
Liver & Biliary System Disorders: gamma-GT increased, cholelithiasis, bilirubinemia, cholangitis;
Metabolic & Nutritional Disorders: hyperglycemia, hypoglycemia, phosphatase alkaline increased, hypercholesterolemia;
Musculoskeletal System Disorders: bursitis, arthritis, tendinitis;
Myo-, Endo-, Pericardial & Valve Disorders: angina pectoris;
Platelet, Bleeding & Clotting Disorders: epistaxis, thrombocytopenia;
Psychiatric Disorders: nervousness, thinking abnormal, concentration impaired, dreaming abnormal, delusion, paranoid reaction;
Reproductive Disorders, Female: breast fibroadenosis;
Reproductive Disorders, Male: impotence, sexual function abnormal;
Resistance Mechanism Disorders: herpes simplex;
Respiratory System Disorders: pneumonia, pharyngitis, sinusitis;
Secondary Terms - Events: inflicted injury;
Skin And Appendages Disorders: pruritus, skin disorder, dermatitis, eczema, dermatitis fungal;
Special Senses Other, Disorders: taste loss;
Urinary System Disorders: urinary incontinence, hematuria, albuminuria, dysuria, nocturia, renal pain;
Vascular (Extracardiac) Disorders: skin cold clammy, claudication intermittent;
Vision Disorders: diplopia, conjunctivitis, cataract, photopsia;
White Cell & Res Disorders: leucopenia.
The following adverse events were reported only once but are considered clinically important: hepatic function test abnormal, hepatic enzymes increased (> 3 times ULN), cholecystitis, allergic reaction, and dopamine dysregulation syndrome.
Myocardial Infarction and Other Ischemic Heart Disease Events
Myocardial infarction and other ischemic heart disease events have been reported with the use of entacapone in combination with levodopa/carbidopa in clinical trials.
In 13 controlled, double-blind studies, 2082 patients (median age of approximately 65) with end-of-dose motor fluctuations ("wearing-off") were treated with entacapone in combination with levodopa/DDC inhibitor and 1582 patients (median age of approximately 65) received levodopa/DDC inhibitor for an average duration of approximately 6 months. The incidence rate of myocardial infarction was 0.53% and 0.32% for entacapone† and levodopa/DDC inhibitor, respectively. Other ischemic heart disease adverse events were reported in 1.54% of patients treated with entacapone and 0.82% of patients treated with levodopa/DDC inhibitor.
† Entacapone refers to entacapone in combination with levodopa/DDC inhibitor
A study was conducted in which patients with early Parkinson’s disease (median age of 61) initiated levodopa treatment with either levodopa/carbidopa in combination with entacapone or levodopa/carbidopa. The average treatment duration was approximately 3 years. Myocardial infarction was reported in 1.9% of patients treated with entacapone compared to 0% of patients treated with levodopa/carbidopa. Other ischemic heart disease adverse events were reported in 1.9% of patients treated with entacapone and in 3.5% of patients who received levodopa/carbidopa. STALEVO is not indicated for the treatment of early Parkinson’s disease.
Entacapone therapy should be administered with caution to patients with ischemic heart disease or risk factors for cardiovascular disease. Periodic evaluation of cardiovascular function is recommended during extended therapy with entacapone.
Prostate Cancer Adverse Events
Prostate cancer has been reported in elderly males during the use of entacapone in combination with levodopa/carbidopa in clinical trials (see WARNINGS AND PRECAUTIONS-Prostate Cancer).
In the study of patients with early Parkinson’s disease who initiated levodopa treatment with either levodopa/carbidopa in combination with entacapone or levodopa/carbidopa (median age of 61), and remained on treatment for an average duration of approximately 3 years, prostate cancer was reported in 3.7% of males treated with levodopa/carbidopa in combination with entacapone and in 0.9% of males treated with levodopa/carbidopa. There was a numerical increase in the probability of developing prostate cancer with increased duration of treatment, but this was not statistically significant. STALEVO is not indicated for the treatment of early Parkinson’s disease.
In 13 controlled, double-blind studies that included patients with end-of-dose motor fluctuations (median age of approximately 65), in which the average treatment duration was approximately 6 months, prostate cancer was reported at similar frequencies in males treated with entacapone (0.31%) and in males treated with levodopa/DDC inhibitor (0.20%).
The clinical relevance of these observations is not known. Physicians are advised to emphasize to patients the importance of adhering to regular examinations for prostate cancer during extended treatment with STALEVO (see WARNINGS AND PRECAUTIONS-Information for Patients).
Abnormal Hematologic and Clinical Chemistry Findings
Slight decreases in hemoglobin, erythrocyte count and hematocrit have been reported during entacapone treatment. The underlying mechanism may involve decreased absorption of iron from the gastrointestinal tract. During long-term treatment (6 months) with entacapone a clinically significant decrease in hemoglobin has been observed in 1.5% of patients.
Post-Market Adverse Drug Reactions
The cumulative exposure of entacapone during the period September 1998 to February 2006 is
estimated as 710, 877 patient years. Voluntary reports of adverse events that have been received since market introduction that are not listed above, are listed in Table 2. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Table 2: Entacapone Post-Market Spontaneous Adverse Event Reports.
| Adverse Event | Frequency | |||
| Common ( 1%) | Uncommon (<1% and 0.1%) | Rare (<0.1% and 0.01%) | Very rare (<0.01%) | |
| Liver and Biliary System Disorders | ||||
| Hepatitis with mainly cholestatic features | X | |||
| Clinically significant increases in liver enzymes | X | |||
| Central and Peripheral Nervous System Disorders | ||||
| Neuroleptic Malignant Syndrome | X | |||
| Gastrointestinal disorders | ||||
| Colitis | X | |||
| Musculoskeletal System Disorders | ||||
| Rhabdomyolysis | X | |||
| Skin and Appendage Disorders | ||||
| Erythematous/maculopapular rash | X | |||
| Urticaria | X | |||
| Skin, hair, beard and nail discoloration | X | |||
Isolated cases of hepatic failure and severe, serious skin reactions resembling erythema multiforme and toxic epidermal necrolysis have been reported in patients treated with entacapone.
Cases of suicidal behavior and bullous conditions have been reported in patients treated with STALEVO.
Isolated cases of angioedema have been reported after initiation of treatment with levodopa/DDC inhibitor/entacapone.
Patients treated with entacapone in combination with levodopa/DDC inhibitor have very rarely reported falling asleep while engaged in activities of daily living, including operation of motor vehicles, which has sometimes resulted in accidents (See WARNINGS AND PRECAUTIONS).
Dopamine Dysregulation Syndrome
Pathological (compulsive) gambling has been reported in post-market data, including those in the literature, for antiparkinson drugs. Impulse control disorders: pathological (compulsive)
gambling, increased libido, hypersexuality, compulsive spending/buying, binge eating/compulsive eating have been reported in patients treated with dopamine agonists and/or other dopaminergic treatments containing levodopa including STALEVO; these were reported at a rate of 0.03 per 1000 patient years. Safety data from various sources including literature, clinical trials, and post-market analysis have described an addictive pattern of dopamine replacement therapy, known as dopamine dysregulation syndrome, in which patients use doses in excess of those required to control their motor symptoms, and was reported at a rate of 0.002 per 1000 patient years. These behavioral symptoms were generally reversible upon dose reduction or treatment discontinuation (see WARNINGS AND PRECAUTIONS, Psychiatric).
DRUG INTERACTIONS
Overview
Protein binding
Entacapone is highly protein bound (98%). In vitro studies have shown that entacapone, at therapeutic concentrations, does not displace drugs of which a large proportion is bound to plasma proteins (e.g. warfarin, salicylic acid, phenylbutazone and diazepam). Entacapone is not markedly displaced by any of these drugs at therapeutic concentrations (see ACTIONS AND CLINICAL PHARMACOLOGY).
Drugs metabolized by Cytochrome P450
Data from in vitro studies using human liver microsomal preparations indicate that entacapone inhibits cytochrome P450 2C9 (IC50 ~ 4 μM).
Other P450 isoenzymes (CYP1A2, CYP2A6, CYP2D6, CYP2E1, CYP3A and CYP2C19) were inhibited only by very high concentrations of entacapone (IC50 from 200 to greater than 1000 μM). The highest concentration of entacapone achieved with an oral 200 mg dose is approximately 5 μM and is not expected to inhibit these enzymes.
Drugs metabolized by Cytochrome P450 (CYP2C9)
Entacapone has been shown to inhibit the activity of cytochrome P450 2C9 in vitro and may potentially interfere with drugs whose metabolism is dependent on this isoenzyme, such as S-warfarin . However, in an interaction study in healthy volunteers, entacapone did not change the plasma levels of S-warfarin, while the AUC for R-warfarin increased on average by 18% [CI90 11-26%]. The INR values increased on average by 13% [CI90 6-19%]. Thus, control of INR is recommended when entacapone treatment is initiated for patients receiving warfarin.
Drugs interfering with biliary excretion
As most entacapone excretion is via the bile, caution should be exercised when drugs known to interfere with biliary excretion, glucuronidation, and intestinal beta-glucuronidase are given concurrently with STALEVO (levodopa, carbidopa and entacapone). These include probenicid, cholestyramine, and some antibiotics (e.g. erythromycin, rifampicin, ampicillin and chloramphenicol).
Drug-Drug Interactions
Drugs metabolized by the Catechol-O-methyltransferase (COMT)
The experience of the clinical use of entacapone with medicinal products that are metabolized by COMT (e.g. catechol-structured compounds: rimiterole, isoprenaline, adrenaline, noradrenaline, dopamine, dobutamine, alpha-methyldopa, apomorphine, and paroxetine) is still limited (see WARNINGS AND PRECAUTIONS). Regardless of their route of administration, including inhalation, drugs known to be metabolized by COMT should be used with caution in patients treated concomitantly with entacapone, as their interaction may result in increased heart rates, possible arrhythmias and excessive changes in blood pressure (see WARNINGS AND PRECAUTIONS).
Non-selective MAO inhibitors
STALEVO should not be given concomitantly with non-selective monoamine oxidase (MAO) inhibitors (e.g. phenelzine and tranylcypromine). The combination of selective MAO-A and selective MAO-B inhibitors is equivalent to non-selective MAO-inhibition, therefore, they should not both be given concomitantly with STALEVO preparations. Non-selective MAO inhibitors must be discontinued at least two weeks prior to initiating therapy with entacapone (See CONTRAINDICATIONS).
Selegiline
In two multiple-dose interaction studies in patients with Parkinson's disease, no interactions between entacapone and selegiline (10 mg) were observed in the presence of coadministered levodopa/DDC inhibitor. More than 400 parkinsonian patients in phase 2 and 3 studies used selegiline in combination with entacapone and levodopa/DDC inhibitor without any apparent interactions. Selegiline should not be used at higher than recommended doses (10 mg/day) when co-administered with STALEVO (also see CONTRAINDICATIONS).
Antihypertensives
Symptomatic postural hypotension may occur when levodopa is initiated in patients already receiving antihypertensives. Dosage adjustment of the antihypertensive agent may be required when STALEVO therapy is started.
Dopamine D2 receptor antagonists (e.g., phenothiazines, butyrophenones, risperidone) and isoniazid
Dopamine D2 receptor antagonists (e.g., phenothiazines, butyrophenones, risperidone) and isoniazid may reduce the therapeutic effects of levodopa.
Phenytoin and papaverine
The beneficial effects of levodopa in Parkinson’s disease have been reported to be reversed by phenytoin and papaverine. Patients taking these drugs with levodopa/carbidopa should be carefully observed for loss of therapeutic response.
Metoclopramide
Although metoclopramide may increase the bioavailability of levodopa by increasing gastric emptying, metoclopramide may also adversely affect disease control by its dopamine receptor antagonistic properties.
Tricyclic antidepressants and noradrenaline re-uptake inhibitors
There have been rare reports of adverse reactions, including hypertension and dyskinesia, resulting from the concomitant use of tricyclic antidepressants and levodopa/carbidopa.
In a single-dose study in healthy volunteers, no interactions between entacapone and imipramine were observed in the absence of coadministration of levodopa/DDC inhibitor.
The potential for interactions between entacapone and tricyclic antidepressants or noradrenaline re-uptake inhibitors has not been systematically evaluated in patients with Parkinson’s disease. The experience on the clinical use of entacapone with tricyclic antidepressants and noradrenaline reuptake inhibitors (desipramine, maprotiline and venlafaxine) is limited. Therefore, patients should be carefully monitored when STALEVO is administered in combination with these drugs.
Iron
Studies have demonstrated that ferrous sulphate decreases the bioavailability of levodopa and/or carbidopa. Also, entacapone may impair the absorption of iron from the gastrointestinal tract. Therefore, STALEVO and iron-containing supplements or multivitamins should be ingested at least 2 to 3 hours apart.
Pyridoxine
STALEVO may be given to patients with Parkinson's disease who are taking vitamin preparations that contain pyridoxine hydrochloride (Vitamin B6).
Anesthetics
When general anesthetics are required STALEVO may be continued for as long as the patient is permitted to take fluids and medication by mouth. If therapy has to be stopped temporarily, STALEVO may be restarted as soon as oral medication can be taken at the same daily dosage as before.
Drug-Food Interactions
Since levodopa competes with certain amino acids, the absorption of STALEVO may be impaired in some patients on a high protein diet.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- As with levodopa/carbidopa, non-selective monoamine oxidase (MAO) inhibitors are contraindicated for use with STALEVO (levodopa, carbidopa and entacapone). These inhibitors must be discontinued at least two weeks prior to initiating therapy with STALEVO. STALEVO may be administered concomitantly with the manufacturer’s recommended dose of MAO inhibitors with selectivity for MAO type B (e.g., selegiline HCl).
For special patient populations see CONTRAINDICATIONS, WARNINGS AND
PRECAUTIONS - Gastrointestinal, Neurologic and Renal.
- STALEVO tablets should not be divided. The tablets should always be swallowed whole.
- STALEVO may be taken with or without food. As with levodopa/DDC, taking STALEVO with a small snack (e.g., biscuits) or liquid may help control gastrointestinal side effects.
Recommended Dose and Dosage Adjustment
The daily dosage must be titrated for each patient to achieve optimal therapeutic response to levodopa. The daily dose should preferably be optimized using one of the five available tablet strengths (50/12.5/200 mg, 75/18.75/200 mg, 100/25/200 mg, 125/31.25/200 mg or 150/37.5/200 mg levodopa/carbidopa/entacapone).
Patients should be instructed to take only one STALEVO tablet at each dosing time. Patients receiving less than 70-100 mg carbidopa a day are more likely to experience nausea and vomiting. The experience with total daily dosage greater than 200 mg carbidopa is limited, the maximum recommended daily dose of entacapone is 1600 mg and therefore the maximum STALEVO dose is 8 tablets per day.
STALEVO is intended mainly for use in patients already receiving treatment with corresponding doses of standard-release levodopa/DDC inhibitor and entacapone.
Starting STALEVO therapy
Switching from levodopa/ DDC inhibitor (carbidopa or benserazide) preparations and entacapone to STALEVO
a. Patients who are currently receiving treatment with entacapone and standard-release levodopa/carbidopa in doses equal to STALEVO tablet strengths can be directly switched to the corresponding STALEVO tablets. For example, patients taking one tablet of 100/25 mg levodopa/carbidopa with one tablet of entacapone 200 mg four times daily can be switched to one 100/25/200 mg STALEVO tablet four times daily.
b. When initiating STALEVO therapy in patients currently receiving treatment with entacapone and levodopa/carbidopa in doses not equal to the available STALEVO tablet strengths (50/12.5/200 mg, 75/18.75/200 mg, 100/25/200 mg, 125/31.25/200 mg or 150/37.5/200 mg), STALEVO dosing should be carefully titrated for optimal clinical response. At the start of therapy, STALEVO should be adjusted to correspond as closely as possible to the total daily dose of levodopa currently used.
c. When initiating STALEVO in patients currently treated with entacapone and levodopa/benserazide in a standard-release formulation, treatment should be stopped for one night and STALEVO therapy started the next morning. The therapy should begin with a dosage of STALEVO that will provide either the same amount of levodopa or slightly (5-10%) more.
Switching in patients not currently treated with entacapone to STALEVO
Initiation of STALEVO at a dosage corresponding to current treatment may be considered in some patients with Parkinson's disease and end-of-dose “wearing-off” who are not stabilised on their current standard-release levodopa/DDC inhibitor treatment. However, a direct switch from levodopa/DDC inhibitor to STALEVO is not recommended for patients who have dyskinesias or whose daily levodopa dose is above 600 mg. In such patients it is advisable to introduce entacapone treatment as a separate medication (entacapone tablets) and adjust the levodopa dose if necessary, before switching to STALEVO.
Entacapone enhances the effects of levodopa, which may cause certain dopaminergic adverse effects e.g., dyskinesias, “on-off” phenomenon, nausea, vomiting, and hallucinations to occur at lower doses and earlier than with preparations containing levodopa alone. It may therefore be necessary, particularly in patients with dyskinesia, to reduce levodopa dosage by 10-30% within the first days to first weeks after initiating STALEVO treatment. The daily dose of levodopa can be reduced by extending the dosing intervals and/or by reducing the amount of levodopa per dose, according to the clinical condition of the patient.
Dosage adjustment during the course of the treatment
When more levodopa is required, an increase in the frequency of doses and/or the use of an alternative strength of STALEVO should be considered, within the dosage recommendations.
When less levodopa is required, the total daily dosage of STALEVO should be reduced either by decreasing the frequency of administration by extending the time between doses, or by decreasing the strength of STALEVO at an administration.
If other levodopa products are used concomitantly with a STALEVO tablet, the maximum dosage recommendations should be followed.
Discontinuation of STALEVO therapy
If STALEVO treatment (levodopa/carbidopa/entacapone) is discontinued and the patient is switched to levodopa/DDC inhibitor therapy without entacapone, it is necessary to adjust the
dosing of other antiparkinsonian treatments, especially levodopa, to achieve a sufficient level of control of the parkinsonian symptoms (see WARNINGS AND PRECAUTIONS).
Missed Dose
If there is more than an hour left until the next dose, the missed dose should be taken immediately and the next tablet at the next scheduled dose. If there is less than an hour until the next dose, the missed dose should be taken immediately and an hour must elapse until the next dose is taken, following which the patient can go back to the normal schedule.
Doses should not be doubled. Always leave at least an hour between STALEVO tablets, to avoid possible side effects.
Administration
Each tablet is to be taken orally either with or without food (see ACTIONS AND CLINICAL PHARMACOLOGY, Pharmacokinetics). One tablet contains one treatment dose. The tablets should always be swallowed whole.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Symptoms:
There are very few cases of overdosage with levodopa reported in the published literature. Based on the limited available information, the acute symptoms of levodopa/DDC inhibitor overdosage can be expected to arise from dopaminergic overstimulation. Doses of a few grams may result in CNS disturbances, with an increasing likelihood of cardiovascular disturbance (e.g., hypotension, tachycardia) and more severe psychiatric problems at higher doses. An isolated report of rhabdomyolysis and another of transient renal impairment suggest that levodopa overdosage may give rise to systemic complications, secondary to dopaminergic overstimulation.
The COMT inhibition by entacapone is dose-dependent. Therefore, a massive overdose of entacapone may produce a 100 % inhibition of COMT enzyme in man, and prevent the metabolism of endogenous and exogenous catechols. The post-marketing data includes isolated cases of overdose in which the reported highest daily dose of levodopa and entacapone has been at least 10,000 mg and 40,000 mg respectively. The acute symptoms and signs in these cases of overdose included agitation, dyskinesia, confusional state, coma, bradycardia, ventricular tachycardia, Cheyne-Stokes respiration, mydriasis, decreased activity, somnolence, hypotonia, discoloration of skin, tongue and conjunctiva, chromaturia, mild renal failure, neuroleptic malignant syndrome and urticaria.
Treatment:
Management of acute overdose with STALEVO (levodopa, carbidopa and entacapone) is the
same as management of acute overdosage with levodopa and entacapone. Pyridoxine is not effective in reversing the actions of STALEVO.
Hospitalization is advised and general supportive measures should be employed, along with immediate gastric lavage and repeated doses of charcoal over time. This may hasten the elimination of entacapone in particular by decreasing its absorption/reabsorption from GI tract. Intravenous fluids should be administered judiciously and an adequate airway maintained.
The adequacy of the respiratory, circulatory and renal systems should be carefully monitored and appropriate supportive measures employed. Electrocardiographic monitoring should be instituted and the patient carefully observed for the possible development of arrhythmias; if required, appropriate antiarrhythmic therapy should be given. The possibility that the patient may have taken other drugs, increasing the risk of drug interations (especially catechol-structured drugs should be taken into consideration). To date, no experience has been reported with dialysis in management of levodopa/carbidopa overdose; hence, its value in overdosage is not known. Hemodialysis or hemoperfusion is unlikely to reduce entacapone levels due to its high binding to plasma protein.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Levodopa
Current evidence indicates that symptoms of Parkinson’s disease are related to depletion of dopamine in the corpus striatum. Administration of dopamine is ineffective in the treatment of Parkinson’s disease apparently because it does not cross the blood-brain barrier. However, levodopa, the metabolic precursor of dopamine, does cross the blood-brain barrier, and presumably is converted to dopamine in the brain. This is thought to be the mechanism whereby levodopa relieves symptoms of Parkinson’s disease.
Carbidopa
When levodopa is administered orally it is rapidly decarboxylated to dopamine in extracerebral tissues so that only a small portion of a given dose is transported unchanged to the central nervous system. Carbidopa does not cross the blood-brain barrier and does not affect the metabolism of levodopa within the central nervous system. Since its decarboxylase inhibiting activity is limited to peripheral tissues, administration of carbidopa with levodopa makes more levodopa available for transport to the brain.
When coadministered with levodopa, carbidopa increases plasma levels of levodopa and reduces the amount of levodopa required to produce a given response by about 75%. Carbidopa prolongs the plasma half-life of levodopa from 50 minutes to 1.5 hours and decreases plasma and urinary dopamine and its major metabolite, homovanillic acid. The Tmax of levodopa, however, was unaffected by the coadministration.
Entacapone
Entacapone is a reversible, selective and mainly peripherally acting inhibitor of catechol-O-methyltransferase (COMT). Entacapone has no antiparkinsonian effect of its own and is designed for concomitant administration with levodopa preparations.
COMT catalyzes the transfer of the methyl group of S-adenosyl-L-methionine to the phenolic group of substrates that contain a cathecol structure. Physiological substrates of COMT include dopa, catecholamines (dopamine, norepinephrine, epinephrine) and their hydroxylated metabolites. In the presence of a decarboxylase inhibitor, COMT becomes the major enzyme which is responsible for the metabolism of levodopa to 3-methoxy-4-hydroxy-l-phenylalanine (3-OMD).
The mechanism of action of entacapone is believed to be related to its ability to inhibit COMT and thereby alter the plasma pharmacokinetics of levodopa. When administered with levodopa and carbidopa, entacapone decreases the degradation of levodopa in the peripheral tissues further by inhibiting the metabolism of levodopa to 3-OMD through the COMT pathway. This leads to more sustained plasma concentrations of levodopa. It is believed that at a given frequency of levodopa administration, these more sustained plasma levels of levodopa result in more constant dopaminergic stimulation in the brain leading to greater effects on the signs and symptoms of Parkinson’s disease. The higher levodopa levels also lead to increased levodopa adverse effects, sometimes requiring a decrease in the dose of levodopa.
When 200 mg entacapone is administered together with levodopa/carbidopa, it increases the area under the curve (AUC) of levodopa by approximately 35% and the elimination half-life of levodopa is prolonged from 1.3 h to 2.4 h. Studies in healthy volunteers and in patients with Parkinson’s disease show that entacapone dose-dependently decreases the formation of 3-OMD from levodopa. The chronic use of entacapone (200 mg, 3 to 10 times daily) in patients with Parkinson’s disease, decreases the AUC of 3-OMD by 42 to 61%.
Pharmacodynamics
In animals, while entacapone enters the CNS to a minimal extent, it has been shown to inhibit central COMT activity. In humans, entacapone inhibits the COMT enzyme in peripheral tissues. The effects of entacapone on central COMT activity in humans have not been studied.
Pharmacokinetics
Pharmacokinetics of STALEVO (levodopa, carbidopa and entacapone)
The pharmacokinetics of levodopa, carbidopa and entacapone following administration of STALEVO tablets have been studied in comparative bioavailability studies in healthy volunteers (see CLINICAL TRIALS-Comparative Bioavailability Studies).
Pharmacokinetics of levodopa, carbidopa and entacapone
Entacapone pharmacokinetics are linear over a dose range of 5 to 200 mg. A slight non linearity
in AUC was seen at doses greater than or equal to 400 mg in a single dose, dose-response, study in patients with Parkinson’s disease. The pharmacokinetics of entacapone are independent of levodopa/carbidopa.
Absorption: There are large intra- and interindividual variations in the absorption of levodopa, carbidopa and entacapone. Both levodopa and entacapone are rapidly absorbed and eliminated.
Entacapone is rapidly absorbed from the GI tract, reaching peak concentrations (Cmax) in the plasma in approximately one hour. Carbidopa is absorbed and eliminated slightly more slowly than levodopa. When given separately without the other two active substances, the bioavailability of levodopa is 15-33%, that of carbidopa 40-70%, and that of entacapone 35% after a 200 mg oral dose. Cmax, after a single 200 mg dose of entacapone, is approximately 1.2 μg/mL. Meals rich in large neutral amino acids may delay and reduce the absorption of levodopa. Food does not affect the absorption of entacapone to any significant extent.
Distribution: The distribution volume of levodopa (Vd 0.36 - 1.6 L/kg) is moderately small; no data are available for carbidopa. The volume of distribution of entacapone at steady state after i.v. injection is small (20L).
Levodopa is bound to plasma proteins only to a minor extent (about 10-30%), while carbidopa is bound approximately 36%, and while entacapone is extensively bound (about 98% over the concentration range of 0.4 to 50 μg/mL), mainly to serum albumin. Entacapone does not distribute widely into tissues due to its high plasma protein binding.
Metabolism: Levodopa is extensively metabolized to various metabolites, decarboxylation by dopa decarboxylase (DDC) and O-methylation by catechol-O-methyltransferase (COMT) being the most important pathways.
Carbidopa is metabolised to two main metabolites which are excreted in the urine as glucuronides and unconjugated compounds. Unchanged carbidopa accounts for 30% of the total urinary excretion.
Entacapone undergoes extensive metabolism, mainly in the liver. The main metabolic pathway of entacapone in humans is the isomerization to the cis-isomer, followed by direct glucuronidation of the parent and cis-isomer; the glucuronide conjugate is inactive. The elimination of entacapone occurs mainly by non-renal metabolic pathways. It is estimated that 80-90% of the dose is excreted in feces, although this has not been confirmed in man. Approximately 10-20% is excreted in urine. Only traces of entacapone are found as unchanged drug in urine. The major part (95 %) of the drug excreted in urine is conjugated with glucuronic acid. Of the metabolites found in urine only about 1 % have been formed through oxidation.
Excretion: Total clearance of levodopa is in the range of 0.55-1.38 L/kg/h. The elimination half-life is (t1/2) 0.6 - 1.3 hours for levodopa and 2 -3 hours for carbidopa, each given separately.
The total body clearance of entacapone, after i.v. administration, is about 800 mL/min. It is eliminated with a short elimination half-life; the half-life for ß-phase being about 0.5 hours and for the γ-phase about 2.5 hours. The ß-phase is predominant, and the γ-phase accounts for
approximately 8 % of the plasma-time-concentration curve (AUC) following i.v. administration.
Due to short elimination half-lives, no true accumulation of levodopa or entacapone occurs on repeated administration.
Special Populations and Conditions
Pediatrics: Safety and effectiveness in pediatric patients have not been established.
Geriatrics: The pharmacokinetics of STALEVO were not studied in Parkinson’s disease patients or in healthy volunteers older than 55 years of age in the comparative bioavailability studies.
In elderly patients given levodopa without carbidopa and entacapone, absorption is greater and elimination is slower than in young subjects. However, when combined with carbidopa, the absorption of levodopa is similar in both elderly and the young patients, although the AUC is still 1.5 times greater in the elderly due to decreased DDC activity and lower clearance caused by aging. Entacapone pharmacokinetics are independent of age.
Gender: The bioavailability of levodopa is significantly higher in women than in men when given with or without carbidopa and/or entacapone (on average, 40% for AUC and 30% for Cmax). No formal gender studies have been conducted with entacapone.
Hepatic Impairment: As there are no clinical trial data to establish a safe and effective dosing regimen for hepatically impaired patients, STALEVO should be not be administered to patients with hepatic impairment (see CONTRAINDICATIONS).
The metabolism of entacapone is slowed in patients with mild to moderate (Child-Pugh grading Class A and B) hepatic impairment caused by cirrhotic disease. In these patients, the AUC and Cmax values were approximately two-fold greater than those in demographically-matched healthy volunteers.
Renal Impairment: STALEVO should be administered cautiously to patients with severe renal disease. There are no studies on the pharmacokinetics of levodopa and carbidopa in patients with renal impairment (see WARNINGS AND PRECAUTIONS).
The pharmacokinetics of entacapone were evaluated in healthy volunteers and in patients with moderately (Clcr 0.60 - 0.89 mL/sec/1.73 m2) and severely (Clcr 0.20 - 0.44 mL/sec/1.73 m2) impaired renal function. After a single oral dose of 200 mg, the pharmacokinetics of entacapone were not significantly changed in patients with moderate to severe renal impairment.
STORAGE AND STABILITY
Store at room temperature (15 - 30°C).
DOSAGE FORMS, COMPOSITION AND PACKAGING
STALEVO (levodopa, carbidopa and entacapone) is supplied as film-coated tablets for oral administration in the following five strengths:
STALEVO 50 mg/12.5 mg/200 mg film-coated tablet containing 50 mg of levodopa, 12.5 mg of carbidopa and 200 mg of entacapone. The brownish- or greyish-red, round, convex, unscored tablets are marked with ‘LCE 50’ on one side. Available in bottles of 100 tablets.
STALEVO 75 mg/18.75 mg/200 mg film-coated tablet containing 75 mg of levodopa, 18.75 mg of carbidopa and 200 mg of entacapone. The light brownish red, oval-shaped, unscored tablets are marked with ‘LCE 75’ on one side. Available in bottles of 100 tablets.
STALEVO 100 mg/25 mg/200 mg film-coated tablet containing 100 mg of levodopa, 25 mg of carbidopa and 200 mg of entacapone. The brownish- or greyish-red, oval-shaped, unscored tablets are marked with ‘LCE 100’ on one side. Available in bottles of 100 tablets.
STALEVO 125 mg/31.25 mg/200 mg film-coated tablet containing 125 mg of levodopa, 31.25 mg of carbidopa and 200 mg of entacapone. The light brownish red, oval-shaped, unscored tablets are marked with ‘LCE 125’ on one side. Available in bottles of 100 tablets.
STALEVO 150 mg/37.5 mg/200 mg film-coated tablet containing 150 mg of levodopa, 37.5 mg of carbidopa and 200 mg of entacapone. The brownish- or greyish-red, elongated-ellipse shaped, unscored tablets are marked with ‘LCE 150’ on one side. Available in bottles of 100 tablets. 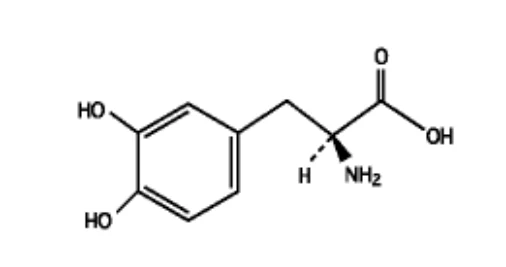
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Levodopa
Proper name: Levodopa
Chemical name: (2S)-2-amino-3-(3,4-dihydroxyphenyl)propanoic acid
Molecular formula and molecular mass: C9H11NO4, 197.2
Structural formula:
Physicochemical properties: Description: White or yellowish-white powder.
Solubilities: slightly soluble in water.
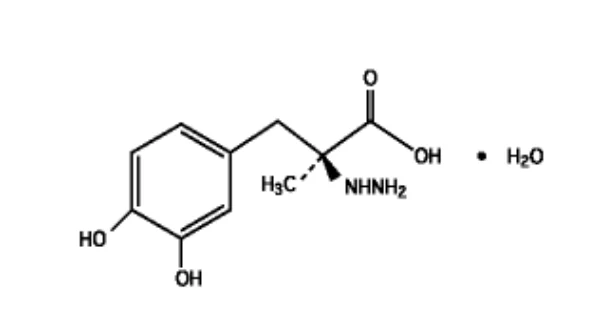
Carbidopa
Proper name: Carbidopa
Chemical name: (-)-L-α-Hydrazino-3,4-dihydroxy-α-methylhydrocynnamic acid monohydrate
Molecular formula and molecular mass: C10H14N2O4–H2O, 244.2
Structural formula:
Tablet content is expressed in terms of anhydrous carbidopa, which has a molecular
weight of 226.2.
Physicochemical properties: Description: white to yellowish-white powder.
Solubilities: slightly soluble in water.
Entacapone
Proper name: Entacapone
Chemical name: (E)-α-Cyano-N,N-diethyl-3,4-dihydroxy-5-nitrocinnamamide
Molecular formula and molecular mass: C14H15N3O5, 305.28
Structural formula:
OH
OH
N
O
CN
CH3
CH3
NO2
Physicochemical properties: Description: yellow or greenish yellow, non-hygroscopic powder.
Solubilities: Practically insoluble in water and in acidic aqueous medium, slightly soluble in organic solvents.
pKa value: approximately 4.5.
Partition coefficient in 1-octanol/phosphate buffer pH 7.4: -
0.25.
Melting point: approximately 163°C.
CLINICAL TRIALS
Entacapone as Adjunct to Levodopa/DDC Inhibitor Therapy
Study demographics and trial design
The effectiveness of entacapone as an adjunct to levodopa/ DDC therapy in the treatment of Parkinson’s disease was demonstrated in three separate 24-week randomized, placebo-controlled, double-blind, multicenter studies in 676 patients with mild to moderate Parkinson's disease (average Hoen and Yahr score: 1.5-3) . In two of these studies (Nordic Study and North American “SEESAW” Study), the patients’ disease was “fluctuating”, i.e. was characterized by documented periods of “On” (periods with relatively good functioning) and “Off” (periods of relatively poor functioning), despite optimum levodopa therapy. In the third trial (German-Austrian “CELOMEN” Study) patients were not required to have been experiencing fluctuations. On average the patients evaluated had been treated with levodopa/ DDC inhibitor therapy for 8.3 years and 86 % were treated with other antiparkinsonian medication (dopamine agonists, selegiline, amantadine, anticholinergics) in addition to a levodopa/DDC inhibitor.
Study results
In the two studies in patients with Parkinson’s disease with documented episodes of end-of-dose motor fluctuations despite optimal levodopa therapy, patients were randomized to receive placebo (n=188) or 200 mg entacapone (n=188) with each daily dose of levodopa/DDC inhibitor (carbidopa or benserazide; average 4 -to- 6 doses per day). The formal double-blind portion of both trials was 6 months. Patients recorded the time spent in the “On” and “Off” states in home diaries periodically throughout the duration of the trial. In the Nordic Study the primary outcome measure was the total mean time spent in the “On” state during an 18-hour diary recorded day, in the North American “SEESAW” study, the primary outcome measure was the proportion of awake time spent over 24 hours in the “On” state.
In addition to the primary outcome measure, as secondary measures, the amount of time spent in the “Off” state was evaluated and patients were also evaluated in subparts of the Unified Parkinson’s Disease Rating Scale (UPDRS), an investigator’s and patients’s global assessment of clinical condition, a 7-point subjective scale designed to assess global functioning in Parkinson’s disease and for change in daily levodopa/DDC dose. Results for the primary efficacy measure for these two studies are shown in Table 3.
Table 3: Primary Outcome Measures: Hours of awake time “On” (Nordic Study) ; Percent of Awake time “On” (North American “SEESAW” study)
| Nordic Study | |||
| Placebo (n=86) Mean (+ SD) | Entacapone (n=85) Mean (+ SD) | Difference | |
| Baseline* | 9.2 + 2.5 | 9.3 + 2.2 | |
| Week 8-24*† | 9.4 + 2.6 | 10.7 + 2.2 | 1h 20 min (8.3%) CI95% 45 min, 1h 56 min |
| North American “SEESAW” Study | |||
| Placebo (n=102) | Entacapone (n=103) | Difference | |
| Baseline** | 60.8 + 14.0 | 60.0 + 15.2 | |
| Week 8-24**‡ | 62.8 + 16.8 | 66.8 + 14.5 | 4.5% (0 h 35 min) CI95% 0.93%, 7.97% |
* daily “On” time (h); † Values represent the average of weeks 8, 16 and 24, by protocol-defined outcome measure. ** Proportion “On” time %; ‡ Values represent the average of weeks 8, 16 and 24, by protocol defined outcome measure.
Effects on “On” time did not differ by age, weight, disease severity at baseline, levodopa dose and concurrent treatment with dopamine agonists or selegiline.
Corresponding significant decreases in “Off” time were also noted. Change from baseline in hours of awake time “Off” in the Nordic Study were: -1.3 hours for the entacapone group; 0 hours for the placebo group and in the North American “SEESAW” Study were: -1.2 hours for the entacapone group; -0.3 for the placebo group.
Withdrawal of entacapone: In the North American “SEESAW” Study, abrupt withdrawal of entacapone, without alteration of the dose of levodopa/carbidopa, resulted in significant worsening of fluctuations, compared to placebo. In some cases, symptoms were slightly worse at baseline, but returned to approximately baseline severity within two weeks following levodopa dose increase on average by 80 mg. In the Nordic Study, similarly, a significant worsening of Parkinsonian symptoms was observed after entacapone withdrawal, as assessed two weeks after drug withdrawal. At this phase the symptoms were approximately baseline severity following levodopa dose increase by about 50 mg.
In the third placebo controlled trial (Austrian-German “CELOMEN” Study), as in the other two trials, patients were randomized to receive 200 mg entacapone or placebo with each dose of levodopa/DDC inhibitor (up to 10 times daily). The CELOMEN study was primarily designed as a safety trial. Measures of effectiveness in this study were the UPDRS Parts II and III and total daily “On” time (see Table 4).
Table 4: Outcome Measures: UPDRS and Hours of awake time “On” (Austrian-German
“CELOMEN” Study)
| UPDRS ADL* | |||
| Placebo (n =104) Mean (+ SD) | Entacapone (n =191) Mean (+SD) | Difference | |
| Baseline | 12.0 + 5.8 | 12.4 + 6.1 | |
| Week 24 | 12.4 + 6.5 | 11.1 + 6.3 | -1.35 CI95 -2.54, -0.16 |
| UPDRS MOTOR* | |||
| Placebo (n = 102 ) | Entacapone (n = 190 ) | Difference | |
| Baseline | 24.1 + 12.1 | 24.9 + 12.9 | |
| Week 24 | 24.3 + 12.9 | 21.7 + 12.1 | -2.83 CI95 -4.95, -0.71 |
| Hours of Awake Time “On” (Home diary)** | |||
| Placebo (n =60) | Entacapone (n =114) | Difference | |
| Baseline | 10.1 + 2.5 | 10.2 + 2.6 | |
| Week 24 | 10.6 + 3.0 | 11.8 + 2.7 | 1.08 CI95 0.13, 2.03 |
*Total population; score change at endpoint
**Fluctuating population, with 5-10 doses
Comparative Bioavailability Studies
Each STALEVO (levodopa, carbidopa and entacapone) tablet, available in five dose strengths, contains levodopa and carbidopa in a 4:1 ratio and a 200 mg dose of entacapone.
The pharmacokinetics of STALEVO tablets have been studied in healthy subjects (age 18 to 55 years old).
| Overall, following administration of corresponding doses of levodopa, carbidopa and | ||
| entacapone as STALEVO or as levodopa/carbidopa product plus COMTAN (entacapone) | ||
| tablets, the mean plasma concentrations of levodopa, carbidopa, and entacapone are comparable. | ||
The results from a comparative bioavailability study investigating the bioavailability of a single oral dose of STALEVO (50 mg levodopa, 12.5 mg carbidopa and 200 mg entacapone; Novartis Pharmaceuticals Canada Inc.) compared to a single oral combined dose of both Sinemet® (50 mg levodopa and 12.5 mg carbidopa; Merck Frosst Canada Ltd.) and COMTAN (200 mg entacapone; Novartis Pharmaceuticals Canada Inc.) in healthy volunteers under fasting conditions are presented below. This was an open-label, single-center, randomized, 2-way crossover, study with forty-two (42) healthy subjects.
Levodopa
(1 x 50 mg)
From measured data
Geometric Mean Arithmetic Mean (CV %)
| Parameter | STALEVO | Sinemet® + COMTAN | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (h*ng/mL) | 896.065 939.884 (33.45) | 872.803 914.310 (32.85) | 102.67 | [98.07; 107.48] |
AUCI (h*ng/mL) | 972.629 1013.94 (31.28) | 947.027 987.248 (30.91) | 102.70 | [98.35; 107.25] |
CMAX (ng/mL) | 445.213 459.350 (24.92) | 485.752 518.574 (37.40) | 91.65 | [82.85; 101.40] |
| TMAX§ (h) | 1.077 (47.28) | 0.903 (64.22) | ||
| T½§ (h) | 1.793 (16.33) | 1.773 (11.22) |
§ Expressed as the arithmetic mean (CV%) only
Carbidopa
(1 x 12,5 mg) From measured data
Geometric Mean Arithmetic Mean (CV %)
| Parameter | STALEVO | Sinemet® + COMTAN | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (h*ng/mL) | 162.001 171.893 (34.25) | 168.262 177.070 (31.91) | 96.28 | [88.88; 104.29]] |
AUCI (h*ng/mL) | 177.042 186.566 (32.17) | 183.233 191.663 (30.09) | 96.62 | [89.56; 104.24] |
CMAX (ng/mL) | 43.322 46.170 (36.22) | 44.973 48.027 (38.23) | 96.33 | [88.75; 104.56] |
| TMAX§ (h) | 2.527 (31.09) | 2.231 (37.00) | ||
| T½§ (h) | 1.962 (31.48) | 1.928 (32.21) |
§ Expressed as the arithmetic mean (CV%) only.
Entacapone
(1 x 200 mg)
From measured data
Geometric Mean Arithmetic Mean (CV %)
| Parameter | STALEVO | Sinemet® + COMTAN | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (h*ng/mL) | 1019.58 1098.69 (37.87) | 1052.74 1137.28 (35.72) | 96.85 | [87.58; 107.10] |
AUCI (h*ng/mL | 1034.85 1115.70 (38.18) | 1066.63 1149.34 (35.28) | 97.02 | [87.83; 107.17] |
CMAX (ng/mL) | 810.413 932.152 (55.34) | 889.291 1002.50 (46.72) | 91.13 | [75.97; 109.31] |
| TMAX§ (h) | 1.351 (87.95) | 1.175 (61.11) | ||
| T½§ (h) | 1.062 (112.58) | 0.910 (67.76) |
§ Expressed as the arithmetic mean (CV%) only.
The pharmacokinetics of the levodopa, carbidopa and entacapone components of STALEVO (50 mg levodopa, 12.5 mg carbidopa and 200 mg entacapone) when taken with food were similar to the pharmacokinetics of levodopa/carbidopa and entacapone when administered concomitantly as separate tablets with food.
DETAILED PHARMACOLOGY
Animal Pharmacology
Levodopa/Carbidopa
Levodopa
Pharmacological experiments in various species of animals have shown that levodopa produced increased motor activity, aggressive behavior and electroencephalographic alerting behavior. However, occasional sedation and ataxia have also been reported in some animal species. Levodopa also reverses the reserpine induced Parkinson-like effects in animals. Cardiovascular studies in dogs and cats have shown that levodopa increases the catecholamine levels in the brain which has been evident in an initial increase in blood pressure followed by a secondary decrease in blood pressure. The changes in blood pressure appear to correlate with the changes in renal function. Biochemical studies in vivo as well as in vitro have demonstrated that levodopa is decarboxylated to dopamine in many tissues. Levodopa crosses the blood-brain barrier and elevates the dopamine concentration in the brain. The dopamine formed can be degraded to
dihydroxyphenylacetic and homovanillic acids which are the two major metabolites in the urine. Dopamine may also be converted to noradrenaline, in which case the major metabolites are vanillylmandelic acid and dihydroxymandelic acid.
Carbidopa
In the absence of biogenic amine precursors, carbidopa is singularly inert pharmacologically. Carbidopa lacks effects upon blood pressure in normal, neurogenic hypertensive, or renal hypertensive dogs. It also does not affect heart rate, exhibit ganglionic, adrenergic, or peripheral anticholinergic properties, or influence renal electrolyte excretion in this species. In mice or rats, carbidopa does not appreciably affect gastric secretion, nor gastric or colonic motility. The compound does not antagonize electroshock or pentylenetetrazol-induced convulsions in mice; neither does it exhibit analgesic activity or affect fixed intervalfixed ratio reinforcement behavior in rats. Overt behavioural effects have not been observed with carbidopa in the rhesus monkey, dog, rat, mouse or pigeon. The dose levels of carbidopa used in the latter investigations were in excess of those necessary to inhibit aromatic amino acid decarboxylase or to alter the actions of levodopa. The studies suggest that carbidopa, when administered alone at dose levels effective in inhibiting aromatic amino acid decarboxylases, lacks appreciable effects upon the cardiovascular, gastrointestinal, renal, or central nervous systems.
Levodopa and Carbidopa Combination
Decarboxylation within peripheral organs and the walls of the brain capillaries limits the portion of an administered dose of levodopa accessible to most central nervous structures. Inhibition of peripheral aromatic amino acid decarboxylase enhances the accumulation of levodopa in the blood and increases the amount of this amino acid available to the brain. If brain decarboxylase is not also inhibited, the result is a marked accumulation of dopamine in the brain. Such a mechanism explains the marked enhancement of brain dopa and dopamine levels which results when levodopa is administered in combination with carbidopa which does not penetrate central nervous system structures even when administered in high doses. Levodopa increases motor activity and irritability, and antagonizes reserpine-induced hypothermia, suppressed locomotion, and ptosis in mice. All these effects are enhanced two- to six-fold by pre-treatment with carbidopa. Increased motor activity induced by levodopa in rats also is enhanced by pre-treatment with carbidopa. In contrast, levodopa-induced vomiting is decreased significantly in dogs and pigeons by pre-treatment with carbidopa.
Entacapone
In vitro
Entacapone is a potent inhibitor of COMT in vitro suppressing COMT activity in crude tissue preparations (brain, duodenum, rat and human red blood cells, liver) with IC50 values ranging from 0.01 μM for rat brain S-COMT to 0.16 μM for rat liver S-COMT. The IC50 values for (Z)-OR-611, the (Z)-isomer of entacapone, were of approximately the same magnitude as those measured for entacapone. The IC50-values for human and rat RBC were similar.
The Ki value, which indicates the affinity of the inhibitor for the enzyme, was 14 nM for rat liver sol-COMT. The enzyme kinetic studies revealed that entacapone is a reversible and selective inhibitor of the COMT enzyme.
Ex vivo
In ex vivo tests, following oral or i.v. administration of entacapone 10 mg/kg, S-COMT was inhibited generally in good correlation with in vitro IC50 values of the same tissue, except the brain which reflects poor penetration of entacapone into the CNS.
In most tissues, inhibition of COMT was transient indicating that entacapone is a reversible COMT inhibitor. In rats, the inhibition of duodenal COMT activity was more complete and sustained as compared to other tissues.
In vivo
Levodopa Pharmacokinetics
Entacapone administered orally at doses of 0.3 - 30 mg/kg, caused a dose-dependent and sustained inhibition of 3-OMD formation from levodopa in rat serum. The inhibition of 3-OMD formation was reflected by elevated levodopa concentrations in serum. Accordingly, addition of entacapone (30 mg/kg) to levodopa/carbidopa treatment prolonged the elimination half-life of levodopa about 5-fold after i.v. levodopa and about 2-fold after oral levodopa.
Peripheral COMT Inhibition and Central Levodopa Metabolism
Entacapone added to the levodopa/carbidopa treatment reduced rat striatal 3-OMD levels and increased both dopamine and levodopa concentrations. Striatal HVA levels were not reduced, supporting the inhibition of peripheral COMT activity by entacapone. Following addition of entacapone to levodopa/carbidopa treatment, the dose of levodopa could be decreased by 70 % and reach the same striatal dopamine concentration as with levodopa/carbidopa alone. A significant reduction in 3-OMD concentration and a significant increase in levodopa concentration were observed with entacapone treatment, indicating that entacapone improved the availability of levodopa in the brain.
Efficacy of entacapone in animal models of Parkinson’s disease
Entacapone significantly improves and sustains the dopaminergic effect of levodopa when given in combination with carbidopa, in various animal models of Parkinson’s disease.
The locomotor activity of hypokinetic reserpine-treated mice was potentiated by the oral administration of entacapone at doses of 3, 10 and 30 mg/kg to the levodopa/carbidopa treatment.
In rats with unilateral 6-hydroxy-dopamine (6-OHDA)-induced lesions of the substantia nigra, entacapone administered orally at doses of 1, 3 and 10 mg/kg potentiated levodopa/carbidopa
induced contralateral circling behavior up to approximately 3 hours post-dosing. In another study, the addition of entacapone, administered orally at dose of 10 mg/kg, to the levodopa/carbidopa treatment allowed a 50% reduction in the levodopa dose without reducing the contralateral turning.
Entacapone, at oral doses of 12.5 mg/kg, significantly increased and potentiated the effect of low dose levodopa/carbidopa in MPTP-treated marmosets.
Special studies
Three short-term studies (8 to 15 days) were conducted in rats to compare the toxicity of entacapone and another COMT inhibitor (tolcapone) at doses ranging from 200 to 600 mg/kg/day. All of these studies examined potential hepatotoxic effects of these two compounds and one was designed to investigate the association of toxicity with uncoupling of oxidative phosphorylation in vivo. Signs of hepatotoxicity (centrilobular hypertrophy, necrosis, vacuolation) were observed in rats treated with tolcapone at doses which caused mortality (400 mg/kg) (plasma exposure at 500 mg/kg/day corresponds to 26 times that in humans at the maximum recommended daily dose of 600 mg); 300 mg/kg may be a threshold dose since 1 of 19 animals exhibited hepatic changes similar to those found at the higher doses. Increased body temperature and changes in mitochondrial respiration and ATP/ADP ratios were found in animals treated with tolcapone (>300 mg/kg) and dinitrophenol, a known uncoupler of oxidative phosphorylation. In contrast, neither hepatotoxic effects (histopathological) nor effects on oxidative phosphorylation were observed with entacapone at any of the doses tested (plasma exposure at the highest dose of 600 mg/kg/day corresponds to 26 times that in humans receiving the maximum recommended daily dose of 1600 mg). The relevance of these findings to man is unknown.
| Treatment | Dose mg/kg | Mortality | Liver Microscopic findings | Body Temp | Mitochondrial ATP/ADP (liver) | Respiratory control ratio | AUC 0-24h h·μg/mL |
| Entacapone | 200 | 0 | none (n=6) | 159 (10x human) | |||
| 300 | 0 | none (n=20) | - | - | - | ||
| 400 | 0 | none (n=5) | - | ||||
| 500 | 0 | none (n=20) | - | - | - | ||
| 600 | 0 | none (n=11) | - | 415 (26x human) | |||
| Tolcapone | 200 | 0 | none (n=6) | 325 (4x human) | |||
| 300 | ↑ | Centrilobular hypertrophy, vacuolation (1/19 animals) | ↑ | ↓ (marginal) | ↓ | ||
| 400 | ↑ | Centrilobular hypertrophy, necrosis, vacuolation (5/5 animals) | ↑ | ||||
| 500 | ↑ | Centrilobular | ↑ | ↓ | ↓ |
| hypertrophy, vacuolation (14/20 animals) | |||||||
| 600 | ↑ | Centrilobular hypertrophy, focal necrosis, vacuolation (9/11 animals) | ↑ | ||||
| Dinitrophenol | 20 | 0 | Centrilobular hypertrophy, necrosis (3/12 animals) | ↑ | ↓ | ↓ |
Blank = not evaluated; - = no different from control; ↑= increase; ↓= decrease
In an in vitro study in rat liver mitochondria, entacapone had no influence on membrane potential at concentrations less than 100 μM, while the other COMT inhibitor (tolcapone) and 2, 4-dinitrophenol caused a concentration-dependent decrease in mitochondrial membrane potential. The results of this study indicate that entacapone does not uncouple oxidative phosphorylation since it had no effect on membrane potential at reasonable concentrations.
Concentration required for 50% decrease in mitochondrial membrane potential in vitro
Entacapone
| Tolcapone | Dinitrophenol |
≥ 100 μM
| 3-5 μM | 2 μM |
TOXICOLOGY
Acute toxicity
Entacapone
| Species | Sex | Dose (mg/kg) | Route | LD50 (mg/kg) |
Mouse Mouse Mouse Mouse | 5 M 5 F 10 F 5 M 5 F | 1000, 1500, 2000 2000 1000, 1500, 2000, 2500 1000, 1500, 2000 1500 | oral oral oral oral | 2000 2000 >2500 >1900 (z-isomer) >1900 (z-isomer) |
Rat Rat Rat | 5 F 5 M 5 M | 1500, 1750, 2000 2000 1000/1000/250-1500/1500/375 (levodopa/benserazide: 2000/500) | oral oral | >2000 entacapone/levodopa/ benserazide:1400/1400/350 levodopa/benserazide:LD50> 2000/500 |
The acute toxicity of the (Z)-isomer is similar to that of (E)-isomer of entacapone and are considered to be low.
Levodopa/Carbidopa
The following table summarizes the acute toxicity data for carbidopa and levodopa alone and in combination. Mortality usually occurred in 12 hours with carbidopa and 30 minutes with levodopa. With the combination of carbidopa and levodopa, deaths occurred between 30 minutes and 24 hours at high doses and up to 12 days with lower doses. The toxicity did not continue to decrease with drug ratios above 1:3.
| Species | Sex | LD50 (mg/kg) | Signs of Toxicity |
| Carbidopa | |||
Mouse Rat (A&W) Rat (I) Mouse (A) | F M M, F F | 4810 5610 2251 1750 | Ptosis, ataxia, decreased activity As above plus bradypnea |
| Levodopa | |||
Rat (A) Rat (A) Mouse | F M F | 2260 1780 1460 | Vocalization, irritability Excitability, increased activity followed by decrased activity |
| Carbidopa/levodopa (1:1) | |||
| Mouse | M, F | 1930† | Erect tail, piloerection, ataxia, lacrimation, increased activity and irritability, clonic convulsion. |
| Carbidopa/levodopa (1:3) | |||
| Mouse | M, F | 3270† | As above |
† Sum of individual dose of carbidopa/levodopa A: Adult
W: Weanling
I: Infant
No distinct organ toxicity was observed in chronic toxicity studies. Entacapone did not increase the toxic effects of levodopa + carbidopa in combination toxicity studies.
Renal Toxicity
In a-1 year toxicity study, entacapone (plasma exposure 20 times that in humans receiving the maximum recommended daily dose of 1600 mg) caused an increased incidence in male rats of nephrotoxicity that was characterized by regenerative tubules, thickening of basement membranes, infiltration of mononuclear cells and tubular protein casts. These effects were not associated with changes in clinical chemistry parameters, and there is no established method for monitoring for the possible occurrence of these lesions in humans. Although this toxicity could represent a species-specific effect, there is not yet evidence that this is so.
Reproductive Studies
Impairment of fertility
Fertility studies in animals have not been conducted with the combination of entacapone, levodopa and carbidopa.
Entacapone
No effect on fertility was observed in male and female rats treated with up to 700 mg/kg/day of entacapone (exposure achieved approximately 28 times higher than that in man after the maximum recommended daily dose of 8 x 200 mg/day).
Levodopa/carbidopa
In reproduction studies with levodopa/carbidopa, no effects on fertility were found in rats receiving doses of approximately two times the maximum daily human dose of carbidopa and four times the maximum daily human dose of levodopa.
Teratogenecity
Entacapone
Entacapone was not teratogenic up to doses of 500 mg/kg twice daily (1000 mg/kg/day), which approximates 100 times higher than the average exposure in man.
The rabbit did not tolerate entacapone as well as the rat, the dose increment being limited by maternal toxicity and only 5 times higher exposure was achieved than the average exposure in man. Increased frequencies of abortions and late/total resorptions and decreased fetal weights were observed in the litters of rabbits treated with maternotoxic doses of 100 mg/kg/day (plasma AUCs 0.4 times those in humans receiving the maximum recommended therapeutic dose of 1600 mg/day) or greater.
Increased incidence of fetal variations was evident in litters from rats treated at the highest dose in the absence of overt maternal toxicity. The maternal plasma drug exposure (AUC) associated with this dose was approximately 34 times the estimated plasma exposure in humans receiving the maximal recommended dose of 8 x 200 mg (1600 mg/day).
When entacapone was administered to female rats prior to mating and during early gestation, an increased incidence of fetal eye anomalies (macrophthalmia, microphthalmia, anophthalmia) was observed in litters of dams treated with doses of 160 mg/kg/day (plasma AUCs 7 times those in humans receiving the maximal recommended daily dose) or greater, in the absence of maternal toxicity. Administration of up to 700 mg/kg/day (plasma AUCs 28 times those in humans receiving the maximal recommended daily dose) to female rats during the later part of gestation and throughout lactation produced no evidence of developmental impairments in the offspring.
Although the teratogenicity of entacapone was assessed in animals, the teratogenic potential of entacapone in combination with levodopa/carbidopa was not assessed.
Maternal treatment with entacapone did not affect the pre- and post-natal development or the subsequent growth development or the fertility of the F1 generation. The exposure achieved in these studies was up to 50 times higher than the average exposure in man.
Levodopa/carbidopa
The incidences of malformations of the heart and great vessels were 0 of 105, 1 of 94, and 6 of 81 fetuses from rabbits given 75, 125 or 250 mg of levodopa/kg/day respectively by the oral route, indicating a dose-dependent teratogenic effect. Anomalies included septal defects, constricted or missing ductus arteriosus, enlarged aortic arches, fused aortas and pulmonary arches, and transpositions. The same types of malformations were also induced in fetuses from rabbits given doses of various combinations of levodopa and carbidopa, but they were not observed when carbidopa was given alone. The malformations, possibly drug-related, were also seen in one mouse fetus from a dam which had received 500 mg of levodopa/kg/day. No drug- induced malformations were observed in fetuses of mice given various combinations of the two drugs or in the offspring of rats given carbidopa. The significance of heart and great vessel malformations in one stunted fetus from a female mouse given the lowest dose of carbidopa (30 mg/kg/day) and in one stillborn pup from a female rat given the mid-dose of the drug combination (10 mg of carbidopa/kg plus 50 mg of levodopa/kg/day) is questionable; both offspring also had other external, cranial and skeletal malformations.
Other effects on reproduction associated with combination treatments in the rabbit included decreased maternal weight gains and fetal weights, and increased resorptions, and incidences of various skeletal anomalies, especially of vertebral centra and skull bones. In mice given the combination product, only a decrease in fetal weight occurred. In rats, none of these effects were observed; the maximal dose administered was 10 mg of carbidopa/kg plus 100 mg of levodopa/kg/day.
Mutagenicity Studies
Entacapone
| STUDY | DOSE-RANGE of entacapone | RESULT | LOWEST POSITIVE DOSE |
Bacterial mutagenicity (S.typh. TA98, TA100, TA1535, TA1537; E. coli WP2 pKM101, WP2 uvrA pKM101); ± S9 | 15.625 - 2000 μg/plate | Negative | |
Mammalian cell mutagenicity (mouse lymphoma L5178Y (Tk+/-) in vitro); " S9 | 2.5 - 400 μg/ml | Positive | At constant concentration range of 25-50 μg/ml |
| DNA-binding in vitro (calf thymus DNA); - S9 | 20, 25 or 50 μg of 14C-entacapone | Negative | |
| Chromosomal aberration in human lymphocytes in vitro; " S9 | 5 - 400 μg/plate | Positive only with S-9 mix | Excluding gaps 400 μg/ml; Including gaps 100 μg/ml |
| Micronuclei in vivo in polychromatic erythrocytes in mice | 40, 200 or 1000 mg/kg orally; 35 mg/kg i.v. | Negative | |
| Rat liver UDS in vivo/in vitro | 600 or 2000 mg/kg, orally | Negative |
Entacapone was not mutagenic in the Ames bacterial mutagenicity tested in four strains of Salmonella typhimurium and two strains of Escherichia coli in the presence and absence of metabolic activation (S-9 mix). Entacapone induced a significant increase in TK mutant frequency in L5178Y mouse lymphoma cells at a concentration range of 25 - 150 μg/mL with or without S-9 mix. The scoring of the number of wells containing small and large colonies showed that the majority of entacapone induced mutants were of the small colony type which indicates a chromosome-type damage of entacapone. In vitro, no substantial amount of entacapone seems to bind to DNA when thymus DNA was exposed to 25 - 50 μg/mL of entacapone. Bacteria, which do not possess chromosomes, were not affected by entacapone. Hence, the negative DNA-binding data is in good correlation with the results of Ames test strengthening the hypothesis that the damage induced by entacapone is at the chromosomal level.
In in vitro chromosomal aberration test with human lymphocytes, entacapone induced increases in chromosomal aberrations only in the presence of S-9 mix. The significant increases in the
frequency of aberrant metaphases were observed at 400 μg/mL (1.3 mM) of entacapone. When mitotic indices were scored, entacapone was more toxic to the cells in the absence of S-9 mix than in its presence, the concentration difference being approximately 5-fold. Observed differences in mitotic indices could be due to differences in the treatment period, i.e. continuous and pulse treatment without and with S-9-mix, respectively.
Entacapone did not induce chromosomal or any other damage which leads to micronucleus formation in polychromatic erythrocytes of treated mice 24, 48 or 72 h after oral administration of a single MTD dose of 1000 mg/kg, or 24 h after a single i.v. dose of 35 mg/kg.
Entacapone in combination with Levodopa/Carbidopa
| STUDY | DOSE-RANGE OF ENTACAPONE | RESULT |
Bacterial mutagenicity (S.typh. TA98, TA100, TA1535, TA1537); ± S9 E coli WP2 pKM101, WP2 uvrA pKM101); ± S9 | 50 - 5000 μg/plate | Negative Negative |
| Micronuclei in vivo in polychromatic erythrocytes in mice | 40, 200 or 1000 mg/kg orally | Negative |
*The ratio of 4:4:1 of entacapone: L-DOPA: carbidopa at each dose-level was employed in the bacterial mutagenicity tests. In the mice micronucleus test L-DOPA 40 mg/kg + carbidopa 10 mg/kg were administered orally, concomitantly with various doses of entacapone.
Combination treatment with levodopa + carbidopa + entacapone was not mutagenic in the Ames bacterial mutagenicity test, tested in four strains of Salmonella typhimurium and two strains of Escherichia coli in the presence and absence of metabolic activation (S-9 mix). The highest dose-level of entacapone was shown to be toxic to the test bacteria.
In mice, entacapone (up to 1000 mg/kg p.o.) did not induce micronuclei in polychromatic erythrocytes when administered concomitantly with levodopa + carbidopa (40 + 10 mg/kg p.o.).
Carbidopa
Carbidopa was positive in the Ames test in the presence and absence of metabolic activation, was mutagenic in the in vitro mouse lymphoma/thymidine kinase assay in the absence of metabolic activation, and was negative in the in vivo mouse micronucleus test.
Carcinogenecity
Entacapone
Two-year carcinogenicity studies of entacapone have been conducted in the mouse at dosages up to 600 mg/kg/day and in the rat at dosages up to 400 mg/kg/day.
In the rat, the only drug-related finding was an increased incidence of renal tubular adenomas and carcinomas noted in males at doses of 400 mg/kg/day. Plasma exposures (AUC) associated with this dose were approximately 20 times higher than estimated plasma exposures of humans receiving the maximum recommended daily dose of entacapone (8 x 200 mg = 1600 mg).
In the mouse study, there was a high incidence of premature mortality in animals receiving the highest dose of entacapone (600 mg/kg/day, corresponding to 10 times higher plasma AUCs than those in humans receiving the maximum recommended daily dose). Thus, the mouse study does not allow adequate assessment of carcinogenicity. Although no treatment related tumors were observed in animals receiving lower doses, the carcinogenic potential of entacapone has not been fully evaluated.
The carcinogenic potential of entacapone in combination with levodopa/carbidopa has not been studied.
Levodopa/carbidopa
In a two-year bioassay of levodopa/carbidopa, no evidence of carcinogenicity was found in rats receiving doses of approximately two times the maximum daily human dose of carbidopa and four times the maximum daily human dose of levodopa.
REFERENCES
- 1. Ahtila S, Kaakkola S, Gordin A, et al. Effect of entacapone, a COMT inhibitor, on the pharmacokinetics and metabolism of levodopa after administration of controlled-release levodopa-carbidopa in volunteers. Clin Neuropharmacol, 1995; 18: 46-57.
- 2. Bernheimer H., Birkmayer W., Hornykiewicz O., Jellinger K., Seitelberger F. Brain dopamine and the syndromes of parkinson and huntington. Clinical, morphological and neurochemical correlations. Journal of the neurological sciences, 1973; 20: 415-455.
- 3. Contin M, Riva R, Martinelli P et al. Effect of age on the pharmacokinetics of oral levodopa in patients with Parkinson’s disease. Eur J Clin Pharmacol, 1991; 41:463-466.
- 4. Illi A., Sundberg S., Koulu M., et al. COMT inhibition by high-dose entacapone does not affect hemodynamics but changes catecholamine metabolism in healthy volunteers at rest and during exercise. Int J Clin Pharmacol Ther, 1994; 32: 582-588.
- 5. Illi A, Sundberg S, Ojala-Karlsson P, Scheinin M, Gordin A. Simultaneous inhibition of catechol-O-methyltransferase and monoamine oxidase A: Effects on hemodynamics and catecholamine metabolism in healthy volunteers. Clin Pharmacol Ther, 1996;59:450-7.
- 6. Illi A, Sundberg S, Ojala-Karlsson P, Scheinin M, Gordin A. Simultaneous inhibition of catecholamine-O-methylation by entacapone and neuronal uptake by imipramine: Lack of interactions. Eur J Clin Pharmacol, 1996;51:273-6.
- 7. Kaakkola S., Wurtman R. Effects of COMT inhibitors on striatal dopamine metabolism: a microdialysis study. Brain Research, 1992; 587: 241-249.
- 8. Kaakkola S, Gordin A, Männistö PT. General properties and clinical possibilities of new selective inhibitors of catechol -O-methyltransferase. Gen Pharmacol, 1994;25:813-24.
- 9. Kaakkola S, Teräväinen H, Ahtila S, Rita H, Gordin A. Effect of entacapone, a COMT inhibitor, on clinical disability and levodopa metabolism in parkinsonian patients. Neurology, 1994;44:77-80.
- 10. Kaakkola S, Teräväinen H, Ahtila S, et al. Entacapone in combination with standard or controlled-release levodopa/carbidopa: a clinical and pharmacokinetic study in patients with Parkinson's disease. Eur J Neurol, 1995;2:341-7.
- 11. Keränen T, Gordin A, Harjola V-P, et al. The effect of catechol-O-methyltransferase inhibition by entacapone on the pharmacokinetics and metabolism of levodopa in healthy volunteers. Clin Neuropharmacol, 1993; 16: 145-156.
- 12.
Keränen T, Gordin A, Karlsson M, et al. Inhibition of soluble catechol-O-methyltransferase and single-dose pharmacokinetics after oral and intravenous administration of entacapone.
Eur J Clin Pharmacol, 1994; 46: 151-157.
- 13.
Kompoliti K, Adler H, Pincus JH et al. Gender differences in levodopa pharmacokinetics.
Neurology, 2001; 56:Suppl 3.
- 14.
Lyytinen J, Kaakkola S, Ahtila S, Tuomainen P, Teräväinen H. Simultaneous MAO-B and
COMT inhibition in L-dopa-treated patients with Parkinson's disease. Movement Disorders, 1997;12:497-505.
- 15. Mannisto P., Tuomainen P. Effects of high single doses of levodopa and carbidopa on brain dopamine and its metabolites: modulation by selective inhibitors of monoamine oxidase and/or catechol-O-methyltransferase in the male rat. Naunnyn Schmiedebgerg's Archives of Pharmacology, 1991; 344: 412-418.
- 16.
Merello M, Lees AJ, Webster R, et al. Effect of entacapone, a peripherally acting catechol-
O-methyltransferase inhibitor, on the motor response to acute treatment with levodopa in patients with Parkinson's disease. J Neurol Neurosurg Psychiatry, 1994; 57: 186-189.
- 17. Myllylä V, Sotaniemi KA, Illi A, et al. Effect of entacapone, a COMT inhibitor, on the pharmacokinetics of levodopa and on cardiovascular reponses in patients with Parkinson's disease. Eur J Clin Pharmacol, 1993; 45: 419-423.
- 18. Nissinen E., Linden I.B., Schultz E., Pohto P. Biochemical and pharmacological properties of a peripherally acting catechol-O-methyltransferase inhibitor entacapone. Naunyn-Schmiedebergs Archives of Pharmacology, 1992; 346: 262-266.
- 19. Nutt JG, Woodward WR, Anderson JL et al. The effect of carbidopa on the pharmacokinetics of intravenously administered levodopa: the mechanism of action in the treatment of parkinsonism. Ann Neurol, 1985; 18:537-543.
- 20. Nutt JG, Woodward WR, Beckner RM, et al. Effect of peripheral catechol-O-methyltransferase inhibition on the pharmacokinetics and pharmacodynamics of levodopa in parkinsonian patients. Neurology, 1994;44:913-9.
- 21.
Nutt JG, Woodward WR, Hammerstad JP et al. The “ON-OFF” Phenomenon in Parkinson’s
Disease. The New England Journal of Medicine, 1984; Vol 310, No. 8: pp 483-488.
- 22. Pinder RM, Brogden RN, Sawyer PR et al. Levodopa and decarboxylase inhibitors: a review of their clinical pharmacology and use in the treatment of parkinsonism. Drugs, 1976; 11:329-377.
- 23. Rizzo V., Memmi M., Moratti R. et al. Concentration of L-dopa in plasma and plasma ultrafiltrates. Journal of Pharmaceutical and Biomedical Analysis, 1996; 14:1043-1046.
- 24.
Ruottinen H, Rinne UK. Effect of one month's treatment with peripherally acting COMT
inhibitor, entacapone, on pharmacokinetics and motor response to levodopa in advanced parkinsonian patients. Clin Neuropharmacol, 1996;19:222-233.
- 25.
Ruottinen HM, Rinne JO, Ruotsalainen UH, et al. Striatal [18F]fluorodopa utilization after
COMT inhibition with entacapone studied with PET in advanced Parkinson's disease. J Neural Transam [P-D Sect], 1995; 10:91-106.
- 26. Ruottinen H, Rinne UK. A double-blind pharmacokinetic and clinical dose-response study of entacapone as an adjuvant to levodopa therapy in advanced parkisonian disease. Clin Neuropharmacol, 1996;19:283-296.
- 27. Ruottinen H, Rinne UK. Entacapone prolongs levodopa response in a one month double blind study in parkinsonian patients with levodopa related fluctuations. J Neurol Neurosurg Psych, 1996;60:36-40.
- 28.
Sawle HM, Burn DJ, Lammertsma AA, et al. The effect of entacapone (OR-611) on brain
[18F]-6-L-fluorodopa metabolism: Implications for levodopa therapy of Parkinson's disease. Neurology, 1994;44:1292-7.
- 29. Sundberg S, Scheinin M, Illi A, et al. The effects of the COMT inhibitor entacapone on haemodynamics and peripheral catecholamine metabolism during exercise. Br J Clin Pharmacol, 1993; 36: 451-456.
- 30. Vickers S, Stuart EK, Bianchine JR et al. Metabolism of carbidopa, an aromatic amino acid decarboxylase inhibitor, in rat, dog, rhesus monkey, and man. Drug Metabolism and Disposition, 1974; Vol 2, No 1 pp 9-22.
- 31. Wikberg T., Vuorela A., Ottoila P., Taskinen J. Identification of major metabolites of the catechol-O-methyltransferase inhibitor entacapone in rats and humans. Drug Metab Dispos Biol Fate Chem, 1993; 21: 81-92.