


Product Monograph - Taro-Clomipramine
RECENT MAJOR LABEL CHANGES
| 1 Indications, 1.1 Pediatrics | 10/2023 |
|---|---|
| 2 Contraindications | 10/2023 |
| 3 Serious Warnings and Precautions Box | 10/2023 |
| 4 Dosage and Administration, 4.1 Dosing Considerations | 10/2023 |
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 10/2023 |
| 7 Warnings and Precautions, Endocrine and Metabolism | 10/2023 |
| 7 Warnings and Precautions, Hematologic | 10/2023 |
| 7 Warnings and Precautions, Musculoskeletal | 10/2023 |
| 7 Warnings and Precautions, Neurologic | 10/2023 |
| 7 Warnings and Precautions, Ophthalmologic | 10/2023 |
| 7 Warnings and Precautions, Peri-Operative Considerations | 10/2023 |
| 7 Warnings and Precautions, Psychiatric | 10/2023 |
| 7 Warnings and Precautions, Skin | 10/2023 |
| 7 Warnings and Precautions, 7.1.3 Pediatrics | 10/2023 |
| 7 Warnings and Precautions, 7.1.4 Geriatrics | 10/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................. 4
1.1 Pediatrics ........................................................................................................................ 4
1.2 Geriatrics ........................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .............................................................. 6
4 DOSAGE AND ADMINISTRATION ................................................................................... 7
4.1 Dosing Considerations .................................................................................................... 7
4.2 Recommended Dose and Dosage Adjustment ................................................................ 8
4.4 Administration .............................................................................................................. 11
4.5 Missed Dose ................................................................................................................. 11
5 OVERDOSAGE ............................................................................................................. 11
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 13
7 WARNINGS AND PRECAUTIONS .................................................................................. 14
7.1 Special Populations ....................................................................................................... 22
7.1.1 Pregnant Women .................................................................................................. 22
7.1.2 Breast-feeding ....................................................................................................... 22
7.1.3 Pediatrics ............................................................................................................... 22
7.1.4 Geriatrics ............................................................................................................... 23
8 ADVERSE REACTIONS .................................................................................................. 23
8.1 Adverse Reactions Overview ........................................................................................ 23
8.2 Clinical Trial Adverse Reactions ......................................................................................... 23
9 DRUG INTERACTIONS .................................................................................................. 27
9.1 Serious Drug Interactions ............................................................................................. 27
9.2 Drug Interactions Overview ......................................................................................... 27
9.3 Drug-Behavioural Interactions .................................................................................... 28
9.4 Drug-Drug Interactions ................................................................................................. 29
9.5 Drug-Food Interactions ................................................................................................. 34
9.6 Drug-Herb Interactions ................................................................................................. 34
9.7 Drug-Laboratory Test Interactions ................................................................................ 34
10 CLINICAL PHARMACOLOGY ......................................................................................... 34
10.1 Mechanism of Action .................................................................................................... 34
10.2 Pharmacodynamics ....................................................................................................... 35
10.3 Pharmacokinetics ......................................................................................................... 37
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 38
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 38
PART II: SCIENTIFIC INFORMATION ........................................................................................ 39
13 PHARMACEUTICAL INFORMATION .............................................................................. 39
14 CLINICAL TRIALS .......................................................................................................... 40
14.3 Comparative Bioavailability Studies .............................................................................. 40
15 MICROBIOLOGY ........................................................................................................... 41
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 41
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 44
PATIENT MEDICATION INFORMATION ................................................................................... 45
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TARO-CLOMIPRAMINE (clomipramine hydrochloride) is indicated for:
- the treatment of depression. TARO-CLOMIPRAMINE also appears to have a mild sedative effect which may be helpful in alleviating the anxiety component often accompanying depression.
the treatment of obsessions and compulsions in patients with obsessive compulsive disorder (OCD). The obsessions and compulsions must cause marked distress, be time-consuming, or significantly interfere with social or occupational functioning.
The effectiveness of clomipramine hydrochloride for long-term use (e.g., for more than 10 weeks) has not been systematically evaluated in placebo-controlled trials. The physician who elects to prescribe TARO-CLOMIPRAMINE for extended periods should periodically re-evaluate the long-term usefulness of the drug for the individual patient (see 4 DOSAGE AND ADMINISTRATION).
1.1 Pediatrics
Depression
Pediatrics (<18 years):
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in children under 18 years of age (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS Clinical Worsening and Suicide Risk).
Obsessive Compulsive Disorder
Pediatrics (<10 years):
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in children under 10 years of age.
Pediatrics (10 to 17 years): Limited information is available for the use of clomipramine hydrochloride in children aged 10 to 17 years, therefore, TARO-CLOMIPRAMINE is not recommended for use in this population (see 4.2 Recommended Dose and Dosage Adjustment, Obsessive Compulsive Disorders, Children and Adolescents).
1.2 Geriatrics
Geriatrics (≥65 years): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 4.2 Recommended Dose and Dosage Adjustment, Depression, Elderly and Debilitated Patients; 4.2 Recommended Dose and Dosage Adjustment, Obsessive Compulsive Disorder, Elderly and Debilitated Patients and 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
TARO-CLOMIPRAMINE (clomipramine hydrochloride) is contraindicated:
- in patients who are hypersensitive to this drug or to other tricyclic antidepressants (TCAs) belonging to the dibenzazepine group or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
in conjunction with, or within fourteen days before or after treatment with a monoamine oxidase inhibitor (MAOI) (see 9.1 Serious Drug Interactions). Hypertensive crises, hyperactivity, hyperpyrexia, spasticity, severe convulsions or coma, and death have been reported in patients receiving MAO inhibitors and TCAs (see 4.1 Dosing Considerations; 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity/Serotonin syndrome; and 9.1 Serious Drug Interactions).
Starting TARO-CLOMIPRAMINE in a patient who is being treated with linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome (see 4.1 Dosing Considerations and 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity/Serotonin syndrome).
- during the acute recovery phase following myocardial infarction and in the presence of acute congestive heart failure (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular; Peri-Operative Considerations and 8.2 Clinical Trial Adverse Reactions, Cardiac disorders).
- in patients with existing liver or kidney damage, or in patients with a history of blood dyscrasias.
- in patients with glaucoma, as the condition may be aggravated due to the atropine-like effects of the drug.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Cardiovascular: Tricyclic antidepressants (TCAs), particularly in high doses, have been reported to produce sinus tachycardia, changes in conduction time and arrhythmias. A few instances of unexpected death have been reported in patients with cardiovascular disorders. Myocardial infarction and stroke have also been reported with drugs of this class. Therefore, TARO-CLOMIPRAMINE should be administered with extreme caution to patients with a history of cardiovascular disorders, especially those with cardiovascular insufficiency, conduction disorders (e.g., atrioventricular block grades I to III) or other arrhythmias, those with circulatory lability and elderly patients (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular). Anticholinergic effects: Because of its anticholinergic properties, TARO-CLOMIPRAMINE should be used with caution in patients with increased intraocular pressure, narrow angle glaucoma or urinary retention, particularly in the presence of prostatic hypertrophy (see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic). Endocrine and Metabolism: Caution should be observed in prescribing TARO-CLOMIPRAMINE for hyperthyroid patients or for patients receiving thyroid medication. Transient cardiac arrhythmias have occurred in rare instances in patients who have been receiving other tricyclic compounds concomitantly with thyroid medication (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism). Seizures: Tricyclic agents are known to lower the convulsive threshold and TARO-CLOMIPRAMINE should, therefore, be used with extreme caution in patients with a history of convulsive disorders and other predisposing factors, e.g., brain damage of varying etiology, concomitant use of neuroleptics, alcoholism and withdrawal from alcohol, and concomitant use with other drugs that lower the seizure threshold. It appears that the occurrence of seizures is dose dependent (see 7 WARNINGS AND PRECAUTIONS, Neurologic). Clinical Worsening and Suicide Risk: Increased risk of self-harm, harm to others, suicidal thinking and behavior with antidepressants use. Closely monitor all antidepressant-treated patients for clinical worsening and for emergence of agitation-type and/or suicidal thoughts and behaviors (see 7 WARNINGS AND PRECAUTIONS, Psychiatric, Clinical Worsening and Suicide Risk). |
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The dosage of TARO-CLOMIPRAMINE (clomipramine hydrochloride) should be individualized according to the requirements of each patient.
- Treatment should be initiated at the lowest recommended dose and increased gradually, noting carefully the clinical response and any evidence of intolerance.
- During the initial dose titration phase, the total daily dose of TARO-CLOMIPRAMINE should be divided and administered with meals to reduce gastrointestinal side effects.
- Owing to the long elimination half-lives of clomipramine hydrochloride and its active metabolite, desmethylclomipramine, steady-state plasma levels may not be achieved until 2 to 3 weeks after a dosage adjustment. It may thus be advisable to wait 2 to 3 weeks after the initial dose titration phase, before attempting further dosage adjustments. Plasma TARO-CLOMIPRAMINE measurement would constitute the optimal guide to dosage monitoring.
- It should be kept in mind that a lag in therapeutic response usually occurs at the onset of therapy, lasting from several days to a few weeks. Increasing the dosage does not normally shorten this latent period and may increase the incidence of side effects.
Note: TARO-CLOMIPRAMINE is not available in 10 mg strength. Lower initial divided doses and small dose adjustments needed for pediatric and geriatric patients can be done using the 10 mg strength from other clomipramine brands.
Cardiovascular
- Prior to initiating treatment with TARO-CLOMIPRAMINE, a cardiac evaluation, including blood pressure and electrocardiogram (ECG) examinations, should be performed, particularly in patients with a history of cardiovascular disorders (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Signs of intolerance and toxicity
- Clinical symptoms of intolerance, especially drowsiness, dizziness, and postural hypotension, should alert the healthcare professional to the need for reduction in dosage. (see 5 OVERDOSAGE).
- The best available evidence of impending toxicity from very high doses of TARO-CLOMIPRAMINE is prolongation of the QRS or QT intervals on the ECG. Prolongation of the PR interval is also significant, but less closely correlated with plasma levels.
- If serious adverse events occur, the dosage should be reduced or treatment altered.
Switching a Patient To or From a Monoamine Oxidase Inhibitor (MAOI) Intended to Treat Psychiatric Disorders
At least 14 days should elapse between discontinuation of a MAOI intended to treat psychiatric disorders and initiation of therapy with TARO-CLOMIPRAMINE. Conversely, at
- least 14 days should be allowed after stopping TARO-CLOMIPRAMINE before starting a MAOI intended to treat psychiatric disorders (see 2 CONTRAINDICATIONS).
Use of TARO-CLOMIPRAMINE With Other MAOIs, Such as Linezolid or Methylene Blue
- Do not start TARO-CLOMIPRAMINE in a patient who is being treated with linezolid or intravenous methylene blue because there is increased risk of serotonin syndrome. In a patient who requires more urgent treatment of a psychiatric condition, other interventions, including hospitalization, should be considered (see 2 CONTRAINDICATIONS).
- In some cases, a patient already receiving TARO-CLOMIPRAMINE therapy may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of serotonin syndrome in a particular patient, TARO-CLOMIPRAMINE should be stopped promptly, and linezolid or intravenous methylene blue can be administered. The patient should be monitored for symptoms of serotonin syndrome for two weeks or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first. Therapy with TARO-CLOMIPRAMINE may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin syndrome).
- The risk of administering methylene blue by non-intravenous routes (such as oral tablets or by local injection) or in intravenous doses much lower than 1 mg/kg with TARO-CLOMIPRAMINE is unclear. The clinician should, nevertheless, be aware of the possibility of emergent symptoms of serotonin syndrome with such use (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin syndrome).
Monitor for agitation, suicidal tendencies.
- Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages, especially when initiating therapy or during any change in dose or dosage regimen. This includes monitoring for agitation-type emotional and behavioural changes (see 7 WARNINGS AND PRECAUTIONS, Psychiatric, Clinical Worsening and Suicide Risk).
4.2 Recommended Dose and Dosage Adjustment
Depression
Initial Dosage
Adults
TARO-CLOMIPRAMINE therapy should be initiated at daily doses of 25 mg. Dosage may be increased by 25 mg increments, as tolerated, at 3 to 4 day intervals up to a total daily dose of 150 mg by the end of 2 weeks. Thereafter, the dose may be gradually increased over a period of several weeks to 200 mg. Doses in excess of 200 mg daily are not recommended for outpatients. Occasionally, in more severely depressed hospitalized patients, dosages up to 300 mg daily may be required.
Elderly and Debilitated Patients
In general, lower dosages are recommended for these patients. Initially, 20 to 30 mg daily in divided doses is suggested, with very gradual increments, depending on tolerance and response. Blood pressure and cardiac rhythm should be checked frequently, particularly in patients who have unstable cardiovascular function.
Note that TARO-CLOMIPRAMINE is not available in 10 mg strength.
Pediatrics (<18 years)
Health Canada has not authorized an indication for pediatric use (<18 years).
Maintenance Dosage
Dosage during maintenance therapy should be kept at the lowest effective level. To minimize daytime sedation during maintenance treatment, the total daily dosage may be given as a single dose at bedtime. Medication should be continued for the expected duration of the depressive episode in order to minimize the possibility of relapse following clinical improvement.
Obsessive Compulsive Disorders
Initial Dosage
Adults
TARO-CLOMIPRAMINE therapy in adult Obsessive Compulsive patients should be initiated at daily doses of 25 mg. Dosage may be increased by 25 mg increments, as tolerated, at 3 to 4 day intervals up to a total daily dose of 100 or 150 mg by the end of 2 weeks. Thereafter, the dose may be gradually increased over a period of several weeks to 200 mg. Doses in excess of 200 mg per day are not generally recommended for outpatients. However, in the treatment of severe cases of Obsessive Compulsive Disorder (OCD), daily doses of up to 250 mg may be required.
Children and Adolescents (10 to 17 years)
Limited information is available for the use of TARO-CLOMIPRAMINE in children aged 10 to 17 years. For this age group, an initial dose of 25 mg per day is recommended. Dosage may be increased by 25 mg increments, as tolerated, at 3 to 4 day intervals. By the end of 2 weeks, patients may be titrated up to 100 to 150 mg per day or 3 mg/kg, whichever is lower. Thereafter, the dose may be gradually increased to 200 mg or 3 mg/kg whichever is lower. A total daily dose above 200 mg should not be used in children or adolescents.
Note that TARO-CLOMIPRAMINE is not available in 10 mg strength.
Pediatrics (<10 years)
Health Canada has not authorized an indication for pediatric use (<10 years).
Elderly and Debilitated Patients
In general, lower dosages are recommended for these patients. Initially, 20 to 30 mg daily in divided doses is suggested, with very gradual increments, depending on tolerance and response. Blood pressure and cardiac rhythm should be checked frequently, particularly in patients who have unstable cardiovascular function.
Note that TARO-CLOMIPRAMINE is not available in 10 mg strength.
Maintenance Dosage (Adults, Children and Adolescents (10 to 17 years))
Double-blind extension phase studies of clomipramine hydrochloride therapy in patients with OCD have followed patients for up to 52 weeks. Although placebo enrollment in these studies was inadequate to permit a controlled comparison, data suggest that TARO-CLOMIPRAMINE therapy can be continued for up to a year without loss of efficacy.
Dosage adjustments may be made during maintenance therapy with the objective of maintaining the patient at the lowest effective dose. To minimize daytime sedation during maintenance treatment, the total daily dosage may be given as a single dose at bedtime. If symptoms recur, the dosage should be increased until the symptoms are controlled. Patients should be reassessed periodically to determine the need for continued treatment. To avoid withdrawal symptoms upon discontinuation of therapy, a gradual decrease in dosage and careful patient monitoring are recommended.
Pediatrics (<10 years)
Health Canada has not authorized an indication for pediatric use (<10 years).
Concomitant use with inhibitors of cytochrome P450 enzymes
Concomitant use of agents in the tricyclic antidepressant (TCA) class (which includes TARO-CLOMIPRAMINE) with drugs that can inhibit cytochrome P450 2D6 (ex: fluoxetine) may require lower doses than usually prescribed for either the tricyclic antidepressant agent or the other drug. Furthermore, whenever one of these drugs is withdrawn from co-therapy, an increased dose of a TCA may be required. It is desirable to monitor TCA plasma levels whenever an agent of the TCA class, including TARO-CLOMIPRAMINE, is going to be co-administered with another drug known to be an inhibitor of P450 2D6 (and/or P450 1A2) (see 9.2 Drug Interactions Overview).
CYP3A and CYP2C inducers
CYP3A and CYP2C inducers, such as rifampicin or anticonvulsants (e.g. barbiturates, carbamazepine, phenobarbital and phenytoin), may decrease clomipramine concentrations as concomitant administration of drugs known to induce cytochrome P450 enzymes, particularly CYP3A4, CYP2C19 may accelerate the metabolism and decrease the efficacy of TARO-CLOMIPRAMINE.
4.4 Administration
TARO-CLOMIPRAMINE capsules should be swallowed whole orally. TARO-CLOMIPRAMINE can be administered with or without food.
4.5 Missed Dose
If the patient misses a dose, instruct the patient to take the dose as soon as they remember. If it is almost time for the next dose, inform the patient to skip the missed dose and continue the regular dosing schedule.
5 OVERDOSAGE
Since children may be more sensitive than adults to acute overdosage with tricyclic antidepressants (TCAs), and since fatalities in children have been reported, effort should be made to avoid potential overdose particularly in this age group.
Deaths by deliberate or accidental overdosage have occurred with this class of drugs. Since the propensity for suicide is high in depressed patients, a suicide attempt by other means may occur during the recovery phase. The possibility of simultaneous ingestion of other drugs should also be considered.
Signs and Symptoms of Overdosage
These may vary in severity depending on various factors such as the amount of drug absorbed, the interval between drug ingestion and start of treatment, and the age of the patient. Accidental ingestion in children should be regarded as serious and potentially fatal.
Signs and symptoms generally appear within 4 hours of ingestion and reach maximum severity after 24 hours. Owing to delayed absorption (increased anticholinergic effect due to overdose), long half-life and enterohepatic recycling of the drug, the patient may be at risk for up to 4 to 6 days.
Signs and symptoms may include drowsiness, stupor, ataxia, vomiting, cyanosis, restlessness, agitation, delirium, severe perspiration, hyperactive reflexes, muscle rigidity, athetoid and choreiform movements, and convulsions. Hyperpyrexia, mydriasis, oliguria or anuria, bowel and bladder paralysis, and respiratory depression may occur.
Hypotension and initial hypertension may occur. However, the usual finding is increasing hypotension which may lead eventually to shock. Serious cardiovascular disturbances are frequently present, including tachycardia, cardiac arrhythmias (flutter, atriofibrillation, premature ventricular beats and ventricular tachycardia) as well as impaired myocardial conduction, atrioventricular and intraventricular block, electrocardiogram (ECG)
abnormalities (such as widened QRS complexes and marked S-T shifts, QTc prolongation), signs of congestive heart failure and cardiac arrest. Coma may ensue.
Treatment of Overdosage
Patients in whom overdosage is suspected should be admitted to hospital without delay. No specific antidote is available and treatment is essentially symptomatic and supportive.
Administration of activated charcoal may help to reduce absorption of the drug. Do not induce vomiting. As TARO-CLOMIPRAMINE is largely protein bound, forced diuresis, peritoneal dialysis and hemodialysis are unlikely to be of value.
Treatment should be designed to ensure maintenance of the vital functions. An open airway should be maintained in comatose patients and assisted ventilation instituted, if necessary, but respiratory stimulants should not be used. Hyperpyrexia should be controlled by external measures, such as ice packs and cooling sponge baths. Acidosis may be treated by cautious administration of sodium bicarbonate. Adequate renal function should be maintained.
ECG monitoring in an intensive care unit is recommended in all patients, particularly in the presence of ECG abnormalities, and should be maintained for several days after the cardiac rhythm has returned to normal. Unexpected deaths attributed to cardiac arrhythmias have been reported several days following an apparent recovery from tricyclic antidepressant overdose. Correction of hypoxia and acidosis, if present, may be beneficial. Correction of metabolic acidosis and low potassium concentrations by means of bicarbonate I.V. and potassium substitution may also be effective for treatment of arrhythmias. If bradyarrhythmia or AV-block occur, consider temporary insertion of a cardiac pacemaker. Because of its effect on cardiac conduction, digitalis should be used only, with caution. If rapid digitalization is required for the treatment of congestive heart failure, special care should be exercised in using the drug.
External stimulation should be minimized to reduce the tendency to convulsions. If convulsions occur, anticonvulsants (preferably intravenous diazepam) should be administered. Barbiturates may intensify respiratory depression, particularly in children, and aggravate hypotension and coma. Paraldehyde may be used in some children to counteract muscular hypertonus and convulsions with less likelihood of causing respiratory depression. If the patient fails to respond rapidly to anticonvulsants, artificial ventilation should be instituted. Prompt control of convulsions is essential since they aggravate hypoxia and acidosis and may thereby precipitate cardiac arrhythmias and arrest.
Shock should be treated with supportive measures, such as intravenous fluids, plasma expanders and oxygen. The use of corticosteroids in shock is controversial and may be contraindicated in tricyclic antidepressant overdose. Hypotension usually responds to elevation of the foot of the bed. Pressor agents (but not epinephrine) should be given cautiously, if indicated. In the event of reduced myocardial function, consider recourse to treatment with dopamine or dobutamine by I.V. drip.
Since it has been reported that physostigmine may cause severe bradycardia, asystole and seizures, its use is not recommended in cases of overdosage with TARO-CLOMIPRAMINE .
Deaths by deliberate or accidental overdosage have occurred with this class of drugs. Since the propensity for suicide is high in depressed patients, a suicide attempt by other means may occur during the recovery phase. The possibility of simultaneous ingestion of other drugs should also be considered.
| For management of a suspected drug overdose, contact your regional poison control Centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration |
| Dosage Form / Strength /Composition | Non-medicinal Ingredients | |
|---|---|---|
| Oral | Capsules 25 mg, 50 mg | Colloidal silicone dioxide, corn starch and magnesium stearate. |
The capsule shell for the 25 mg contains iron oxide black, D&C Yellow 10, FD&C Blue No. 2, FD&C Red No. 3, titanium dioxide, sodium lauryl sulfate, gelatin, black ink SW-9008 and black ink SW-9010.
The capsule shell for the 50 mg contains iron oxide yellow, titanium dioxide, sodium lauryl sulfate, gelatin, black ink SW-9008 and black ink SW-9010.
The black ink SW-9008 contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, purified water, strong ammonia solution, potassium hydroxide and black iron oxide.
The black ink SW-9010 contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, purified water, strong ammonia solution and black iron oxide.
TARO-CLOMIPRAMINE (clomipramine hydrochloride) 25 mg: Hard gelatin capsule, size 2, dark blue cap and light blue body. “CLOM 25” printed in black ink on both cap and body. Contains loose white powder.
TARO-CLOMIPRAMINE (clomipramine hydrochloride) 50 mg: Hard gelatin, yellow opaque capsule, size 1. “CLOM 50” printed in black ink on both cap and body. Contains loose white powder.
All strengths are available in bottles of 30 and 90 capsules.
Note that TARO-CLOMIPRAMINE is not available in 10 mg strength. Lower initial divided doses and small dose adjustments needed for pediatric and geriatric patients can be done using the 10 mg strength from other clomipramine brands.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Cardiovascular
TARO-CLOMIPRAMINE is contraindicated in the acute recovery period following myocardial infarction or in cases of acute congestive heart failure.
Extreme caution should be used when TARO-CLOMIPRAMINE is given to patients with:
- thyroid disease or those taking thyroid medication, because of the possibility of cardiovascular toxicity, including arrhythmias;
- cardiovascular disease.
Tricyclic antidepressants (TCAs), particularly in high doses, have been reported to produce sinus tachycardia, changes in conduction time, arrhythmias and severe hypotension. Cardiac arrhythmias and severe hypotension may also occur at normal doses in patients with pre-existing cardiovascular disease. TARO-CLOMIPRAMINE also has a hypotensive action which may be detrimental in these circumstances. In such cases, treatment should be initiated at low doses with progressive increases only if required and tolerated, and the patients should be under close surveillance at all dosage levels. Monitoring of cardiac function and the electrocardiogram (ECG) is indicated in such patients as well as in the elderly (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory test).
A few instances of unexpected death have been reported in patients with cardiovascular disorders. Myocardial infarction and stroke have also been reported with drugs of this class (see 8.2 Clinical Trial Adverse Reactions, Cardiac disorders). Therefore, TARO-CLOMIPRAMINE should be administered with extreme caution to patients with a history of cardiovascular disorders, especially those with cardiovascular insufficiency, conduction disorders (e.g., atrioventricular block grades I to III) or other arrhythmias, those with circulatory lability and elderly patients (see 2 CONTRAINDICATIONS).
There may be a risk of QTc prolongation at supra-therapeutic doses or supra-therapeutic plasma concentrations of clomipramine, as occur in the case of co-medication with selective serotonin reuptake inhibitors (SSRIs). It is established that hypokalemia is a risk-factor of QTc prolongation and Torsades de pointes. Therefore, hypokalemia should be treated before initiating treatment with TARO-CLOMIPRAMINE and TARO-CLOMIPRAMINE should be used with caution when combined with SSRIs or diuretics
TARO-CLOMIPRAMINE is not available in 10 mg strength. Lower initial divided doses and small dose adjustments needed for pediatric and geriatric patients can be done using the 10 mg strength from other clomipramine brands (see 4 DOSAGE AND ADMINISTRATION section).
ECG abnormalities have been observed in patients treated with TARO-CLOMIPRAMINE. The most common ECG changes were premature ventricular contractions (PVCs), ST-T wave changes, and abnormalities in intraventricular conduction. These changes were rarely associated with significant clinical symptoms. Nevertheless, caution is necessary when treating patients with heart disease, as well as elderly subjects. In these patients, cardiac function should be monitored and ECG examinations performed during long-term therapy. Gradual dose titration is also recommended.
Dental Effects
Lengthy treatment with TCAs can lead to an increased incidence of dental caries.
Dependence/Tolerance
Withdrawal Symptoms: A variety of withdrawal symptoms have been reported in association with abrupt discontinuation of TARO-CLOMIPRAMINE, including dizziness, nausea, vomiting, headache, malaise, sleep disturbance, hyperthermia and irritability. In addition, such patients may experience a worsening of psychiatric status. While the withdrawal effects of TARO-CLOMIPRAMINE have not been systematically evaluated in controlled trials, they are well known with closely related TCAs. It is recommended that the dosage be tapered gradually and the patient monitored carefully during discontinuation.
Driving and Operating Machinery
Since TARO-CLOMIPRAMINE may produce sedation, particularly during the initial phase of therapy, patients should be cautioned about the danger of engaging in activities requiring mental alertness, judgement and physical coordination.
Endocrine and Metabolism
Caution should be observed in prescribing TARO-CLOMIPRAMINE for hyperthyroid patients or for patients receiving thyroid medication (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Endocrine and Metabolism). Transient cardiac arrhythmias have occurred in rare instances in patients who have been receiving other tricyclic compounds concomitantly with thyroid medication.
As with certain other psychotherapeutic drugs, TARO-CLOMIPRAMINE elevates prolactin levels. Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of TARO-CLOMIPRAMINE is contemplated in a patient with a previously detected breast cancer. Although disturbances such as galactorrhea, amenorrhea, gynecomastia, and impotence have been reported, the clinical significance of elevated serum prolactin levels is unknown for most patients. An increase in mammary neoplasms has been found in rodents after chronic administration of neuroleptic drugs. Neither clinical studies nor epidemiologic studies conducted to date, however, have shown an association between chronic administration of these drugs and mammary tumorigenesis; the available evidence is considered too limited to be conclusive at this time.
TCAs have been associated with porphyrinogenicity in susceptible patients.
Hyponatremia: Hyponatremia has occurred as a result of treatment with clomipramine (see 8.5 Post-Market Adverse Reactions, Metabolism and Nutrition Disorders). In many cases, hyponatremia appears to be the result of the syndrome of inappropriate antidiuretic hormone secretion (SIADH). Elderly patients may be at greater risk of developing hyponatremia with a serotonergic antidepressant. Also, patients taking diuretics or who are otherwise volume-depleted can be at greater risk. Discontinuation of TARO-CLOMIPRAMINE in patients with symptomatic hyponatremia and appropriate medical intervention should be instituted. Signs and symptoms of hyponatremia include headache, difficulty concentrating, memory impairment, confusion, weakness, and unsteadiness, which can lead to falls. More severe and/or acute cases have included hallucination, syncope, seizure, coma, respiratory arrest, and death.
Lactose: TARO-CLOMIPRAMINE contains lactose monohydrate. Patients with hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this product.
Gastrointestinal
The more common adverse reactions of TARO-CLOMIPRAMINE involve anticholinergic effects, including effects on the gastrointestinal system, such as dry mouth, and constipation.
TCAs may give rise to paralytic ileus, particularly in the elderly and in hospitalized patients. Therefore, appropriate measures should be taken if constipation occurs.
Hematologic
Isolated cases of bone marrow depression with agranulocytosis have been reported. Leukocyte and differential blood cell counts are recommended in patients receiving treatment with TARO-CLOMIPRAMINE over prolonged periods, and should be performed for patients who develop fever, an influenzal infection, or sore throat. In the event of an allergic skin reaction, TARO-CLOMIPRAMINE should be withdrawn.
Because TARO-CLOMIPRAMINE is highly bound to serum protein, the administration of TARO-CLOMIPRAMINE to patients taking other drugs that are highly bound to protein (e.g., warfarin, digoxin) may cause an increase in plasma concentrations of these drugs, potentially resulting in adverse effects (see 9.4 Drug-Drug Interactions). Conversely, adverse effects may result from displacement of protein bound TARO-CLOMIPRAMINE by other highly bound drugs. Therefore, caution is advised in patients with a history of a bleeding disorder.
Hepatic /Biliary/Pancreatic
TARO-CLOMIPRAMINE is contraindicated in patients with existing liver damage (see 2 CONTRAINDICATIONS).
Clomipramine hydrochloride has occasionally been associated with elevations in SGOT (AST) and SGPT (ALT) of potential clinical significance (e.g., values greater than 3 times the upper limit of normal).
In the majority of cases, these enzyme elevations were not associated with other clinical findings suggestive of hepatic injury.
Isolated cases of obstructive jaundice have been reported. Caution is indicated in treating patients with known liver disease and periodic monitoring of hepatic function is recommended in such patients.
Immune
In the event of an allergic skin reaction, TARO-CLOMIPRAMINE should be withdrawn.
Monitoring and Laboratory Tests
Before initiating treatment, it is advisable to check the patient's blood pressure, because individuals with hypotension or a labile circulation may react to the drug with a fall in blood pressure. Regular measurements of blood pressure should be performed in susceptible patients. Postural hypotension may be controlled by reducing the dosage or administering circulatory stimulants.
Cardiac function, including blood pressure and ECG, should be periodically monitored before and during treatment with TARO-CLOMIPRAMINE, particularly in patients with a history of cardiovascular disorders (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
The blood count should be monitored during treatment with TARO-CLOMIPRAMINE (especially if the patient develops fever, sore throat or other symptoms which are associated with influenza infection), since isolated cases of agranulocytosis have been associated with the use of TCAs (see 7 WARNINGS AND PRECAUTIONS, Hematologic). This is particularly relevant during the first few months of therapy and during prolonged treatment.
In patients with hepatic and renal disease or a history of liver disease, periodic monitoring of the hepatic enzyme levels and renal function is recommended (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; Renal; and 8.2 Clinical Trial Adverse Reactions).
Musculoskeletal
Epidemiological studies, mainly conducted in patients 50 years of age and older, show an increased risk of bone fractures in patients receiving SSRIs and TCAs. The mechanism leading to this risk is unknown. Elderly patients may be at greater risk of developing hyponatremia with a serotonergic antidepressant, which is associated with weakness, and unsteadiness, and can lead to falls (see 7 WARNINGS AND PRECAUTIONS, Hyponatremia).
Neurologic
Seizure: Tricyclic agents are known to lower the convulsive threshold and TARO-CLOMIPRAMINE (clomipramine hydrochloride) should, therefore, be used with extreme caution in patients with a history of convulsive disorders and other predisposing factors, e.g., brain damage of varying etiology, concomitant use of neuroleptics, alcoholism and withdrawal from alcohol, and concomitant use with other drugs that lower the seizure threshold. It appears that the occurrence of seizures is dose dependent. Therefore, the recommended total daily doses should not be exceeded (see 4.2 Recommended Dose and Dosage Adjustment).
Electroconvulsive Therapy (ECT): Concurrent administration of electroconvulsive therapy and TARO-CLOMIPRAMINE may be hazardous and such treatment should be limited to patients for whom it is essential. Healthcare professionals should discuss with patients the risk of taking TARO-CLOMIPRAMINE while engaging in activities in which a sudden loss of consciousness could result in serious injury to the patient or others e.g., the operation of complex machinery, driving, swimming, or climbing.
Central Nervous System: Hyperthermia cases occurred when clomipramine hydrochloride was used in combination with other drugs. Cases were considered to be neuroleptic malignant syndrome when clomipramine hydrochloride and a neuroleptic were used concomitantly. (see 8.5 Post-market Adverse Reactions, Central Nervous System).
Serotonin toxicity / Serotonin syndrome: Serotonin toxicity, also known as serotonin syndrome, is a potentially life-threatening condition and has been reported with TCAs including clomipramine hydrochloride, particularly during combined use with other serotonergic drugs (see 9 DRUG INTERACTIONS).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus
If concomitant treatment with TARO-CLOMIPRAMINE and other serotonergic agents, is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. (see 2 CONTRAINDICATIONS, 4.1 Dosing Considerations, and 9.4 Drug-Drug Interactions). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Concomitant Use with Monoamine Oxidase Inhibitors (MAOI) including Linezolid and Intravenous Methylene Blue:
The concomitant use of TARO-CLOMIPRAMINE with MAOIs intended to treat psychiatric disorders is contraindicated. TARO-CLOMIPRAMINE should also not be started in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue (see 9.1 Serious Drug Interactions). All reports with methylene blue that provided information on the route of administration involved intravenous administration in the dose range of 1 mg/kg to 8 mg/kg. No reports involved the administration of methylene blue by other routes (such as oral tablets or local tissue injection) or at lower doses. There may be circumstances when it is necessary to initiate treatment with a MAOI such as linezolid or intravenous methylene blue in a patient taking TARO-CLOMIPRAMINE. TARO-CLOMIPRAMINE should be discontinued before initiating treatment with the MAOI (see 2 CONTRAINDICATIONS and 4.1 Dosing Considerations).
Ophthalmologic
Angle-closure Glaucoma: As with other antidepressants, TARO-CLOMIPRAMINE can cause mydriasis, which may trigger an angle closure attack in a patient with anatomically narrow ocular angles (see 8.2 Clinical Trial Adverse Reactions). Patients should be examined to determine whether they are susceptible to angle-closure and be informed to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Anticholinergic effects: Because of its anticholinergic properties, TARO-CLOMIPRAMINE should be used with caution in patients with increased intraocular pressure, or narrow angle glaucoma or disturbances of visual accommodation (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Lacrimation: Decreased lacrimation and accumulation of mucoid secretions, due to the anticholinergic properties of TCAs, may cause damage to the corneal epithelium in patients with contact lenses.
Peri-Operative Considerations
TARO-CLOMIPRAMINE is contraindicated in the acute recovery period following myocardial infarction (see 2 CONTRAINDICATIONS). TARO-CLOMIPRAMINE should be discontinued as soon as possible prior to elective surgery because of possible cardiovascular effects. Hypertensive episodes have been observed during surgery in patients taking TARO-CLOMIPRAMINE (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Psychiatric
Clinical Worsening and Suicide Risk:
It is important that TARO-CLOMIPRAMINE be dispensed in the least possible quantities to depressed out-patients, since suicide has been accomplished with this class of drug.
Pediatrics, Placebo-Controlled Clinical Trial Data: Analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer antidepressants suggest that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo. TARO-CLOMIPRAMINE is not indicated for use in pediatric patients under 10 years of age (see 1.1 Pediatrics).
Adults and Pediatrics: Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages given any antidepressant drug. This includes monitoring for emotional and behavioural changes. Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide. There has been a longstanding concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment.
The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychiatric. Although a causal link between the emergence of such symptoms and either the worsening of depression and/or the emergence of suicidal impulses has not been established, there is concern that such symptoms may represent precursors to emerging suicidality.
All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases.
Consideration should be given to changing the therapeutic regimen, including possibly discontinuing the medication, in patients whose depression is persistently worse, or who are experiencing emergent suicidality or symptoms that might be precursors to worsening depression or suicidality, especially if these symptoms are severe, abrupt in onset, or were not part of the patient’s presenting symptoms.
Patients, families and caregivers of patients being treated with antidepressants for major depressive disorder or other indications, both psychiatric and nonpsychiatric, should be alerted about the emergence of agitation, irritability, unusual changes in behavior, and the other symptoms described above, as well as the emergence of suicidality, and to report such symptoms immediately to healthcare professionals. Such monitoring should include daily observation by families and caregivers.
Screening Patients for Bipolar Disorder: A major depressive episode may be the initial presentation of bipolar disorder. Prior to initiating treatment with an antidepressant, patients with depressive symptoms should be adequately screened to determine if they are at risk for bipolar disorder; such screening should include a detailed psychiatric history, including a family history of suicide, bipolar disorder, and depression. It should be noted that TARO-CLOMIPRAMINE is not approved for use in treating bipolar depression.
Psychosis, Confusion, and Other Neuropsychiatric Phenomena: Patients treated with clomipramine hydrochloride have been reported to show a variety of neuropsychiatric signs and symptoms including delusions, hallucinations, psychotic episodes, confusion, and paranoia. Because of the uncontrolled nature of many of the studies, it is impossible to provide a precise estimate of the extent of risk imposed by treatment with TARO-CLOMIPRAMINE. In patients treated with TCAs, activation of latent schizophrenia or aggravation of existing psychotic manifestations in schizophrenic patients may occur. Hyperactive or agitated patients may become over-stimulated. A reduction in dose or discontinuation of TARO-CLOMIPRAMINE should be considered under these circumstances.
In predisposed and elderly patients, TCAs may, particularly at night, provoke pharmacogenic (delirious) psychoses that disappear within a few days of withdrawing the drug.
Mania/Hypomania: Patients with manic-depressive tendencies may experience hypomanic or manic shifts.
Renal
TARO-CLOMIPRAMINE is contraindicated in patients with existing liver or kidney damage (see 2 CONTRAINDICATIONS).
It is advisable to monitor renal function during long-term therapy with TCAs.
Caution is called for when employing TARO-CLOMIPRAMINE in patients with tumors of the adrenal medulla (e.g., pheochromocytoma, neuroblastoma), in whom the drug may provoke hypertensive crisis.
Because of its anticholinergic properties, TARO-CLOMIPRAMINE should be used with caution in patients with urinary retention.
Reproductive Health: Female and Male Potential
Teratogenic Risk
No teratogenic effects were observed in rats and mice at doses up to 20 times the maximum daily human dose. Slight nonspecific fetotoxic effects were seen in the offspring of pregnant mice given doses 10 times the maximum daily human dose. Slight nonspecific embryotoxicity was observed in rats given doses 5 to 10 times the maximum daily human dose.
Skin
DRESS: Rare cases of drug rash with eosinophilia and systemic symptoms (DRESS), a potentially life-threatening adverse drug reaction, have been reported with the use of clomipramine. Symptoms include skin rashes or eruption, fever, eosinophilia, atypical lymphocytosis, swollen lymph nodes, inflammation of internal organs. In the event of severe acute reactions such as DRESS, discontinue clomipramine therapy immediately and institute appropriate treatment.
7.1 Special Populations
7.1.1 Pregnant Women
The safety of use in pregnant women has not been established. Therefore, TARO-CLOMIPRAMINE should not be administered to women of childbearing potential, or during pregnancy, unless, in the opinion of the healthcare professionals, the expected benefit to the patient outweighs the potential risk to the fetus. Withdrawal symptoms including tremors, dyspnea, lethargy, colic, irritability, hypotonia/ hypertonia, convulsions and respiratory depression have been reported in neonates whose mothers received TCAs during the third trimester of pregnancy. To avoid such symptoms, TARO-CLOMIPRAMINE should, if possible, be gradually withdrawn at least 7 weeks before the calculated date of confinement.
7.1.2 Breast-feeding
Since clomipramine passes into breast milk, TARO-CLOMIPRAMINE should be gradually withdrawn or the infant weaned if the patient is breast-feeding.
7.1.3 Pediatrics
Depression
Pediatrics (<18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in children under 10 years of age.
Obsessive Compulsive Disorder
Pediatrics (<10 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in children under 10 years of age.
Pediatrics (10 to 17 years): Limited information is available for the use of clomipramine hydrochloride in children aged 10 to 17 years, therefore, TARO-CLOMIPRAMINE is not recommended for use in this population. The long-term effects of clomipramine hydrochloride on childhood growth and development have not been determined. (see 4.2 Recommended Dose and Dosage Adjustment, Obsessive Compulsive Disorders, Children and Adolescents).
7.1.4 Geriatrics
Evidence from clinical studies and experience suggests that use of clomipramine hydrochloride in the geriatric population is associated with differences in safety or effectiveness. Lower dosages are recommended for elderly and debilitated patients (see 4.2 Recommended Dose and Dosage Adjustment, Depression, Elderly and Debilitated Patients and 4.2 Recommended Dose and Dosage Adjustment, Obsessive Compulsive Disorder, Elderly and Debilitated Patients Cardiovascular side effects may be reflected in ECG changes, which are seen most frequently in elderly patients, as is postural hypotension. The elderly are more prone to confusional states (see 8.2 Clinical Trial Adverse Reactions, Psychiatric disorders).
Clomipramine hydrochloride has been associated with cases of clinically significant hyponatremia. Elderly patients may be at greater risk for this adverse reaction (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hyponatremia).
8 ADVERSE REACTIONS
8.1 Adverse Reactions Overview
The most commonly observed adverse events associated with the use of clomipramine hydrochloride and not seen at an equivalent incidence among placebo-treated patients were gastrointestinal complaints, including dry mouth, constipation, nausea, dyspepsia, and anorexia; nervous system complaints, including somnolence, tremor, dizziness, nervousness and myoclonus; genitourinary complaints including changed libido, ejaculatory failure, impotence and micturition disorder; and other miscellaneous complaints, including fatigue, sweating, increased appetite, weight gain, and visual changes.
If severe neurological or psychiatric reactions occur, TARO-CLOMIPRAMINE should be withdrawn.
Elderly patients are particularly susceptible to anticholinergic, psychiatric, neurological and cardiovascular effects.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following adverse reactions have also been reported with clomipramine or other tricyclic antidepressants (TCAs).
(Frequency estimates: Very common >10%; Common >1 to 10%; Rare >0.01 to 1%; Very rare <0.01%)
Blood and lymphatic system disorders
Very rare: agranulocytosis, eosinophilia, leukopenia, purpura and thrombocytopenia may occur as an idiosyncratic response. One case of pancytopenia has been reported.
Cardiovascular
Very common: sinus tachycardia.
Common: arrhythmia, palpitation, syncope.
Very rare: congestive heart failure, myocardial infarction, heart block, asystole, stroke, disturbances in cardiac conduction (e.g., widening of QRS complex, PQ changes, bundle-branch block, prolonged QT interval, Torsade de points in hypokalemia).
Ear and labyrinth disorders
Very rare: tinnitus.
Endocrine Disorders
Very rare: gynecomastia in the male, galactorrhea in the female, inappropriate antidiuretic hormone (SIADH) secretion syndrome, menstrual irregularity.
Eye disorders
Very common: disturbances of visual accommodation.
Very rare: mydriasis, glaucoma.
General disorders and administration site conditions
Very common: hot flushes.
Very rare: drug fever, weakness, hyperpyrexia.
Gastrointestinal disorders
Very common: dry mouth and rarely associated sublingual adenitis.
Common: vomiting, abdominal cramps.
Rare: diarrhea.
Very rare: bitter taste, stomatitis, epigastric distress, black tongue, dysphagia, increased salivation, paralytic ileus.
Hepatobiliary disorders
Very rare: hepatitis with or without jaundice, obstructive jaundice.
Immune system disorders
Very rare: edema (general or of face and tongue), allergic alveolitis (pneumonia) with or without eosinophilia, systemic anaphylactic/anaphylactoid reactions including hypotension.
Investigations
Very common: electrocardiogram (ECG) changes (including flattening or inversion of T wave, depressed S-T segments) in patients of normal cardiac status.
Rare: elevated transaminases.
Very rare: alterations in EEG patterns, elevation or depression of blood sugar levels, increase in prolactin levels, weight loss.
Nervous system disorders
Common: headache, paresthesia (numbness, tingling sensation, symptoms suggestive of peripheral neuropathy), muscle hypertonia, muscle weakness.
Rare: epileptic seizures.
Very rare: incoordination, ataxia, extrapyramidal symptoms, speech disorders.
Psychiatric disorders
Common: delirium, drowsiness, insomnia, confusional states with hallucinations (particularly in geriatric patients and patients suffering from Parkinson’s disease), anxiety, agitation, restlessness, sleep disturbances, nightmares, aggravated depression, hypomania, mania, decrease in memory, feeling of unreality, depersonalization, disorientation.
Rare: activation of latent psychosis.
Very rare: aggressiveness.
Renal and urinary disorders
Common: dilation of the urinary tract.
Reproductive system and breast disorders
Very rare: breast enlargement and galactorrhea in the female, testicular swelling, menstrual irregularity.
Respiratory thoracic and mediastinal disorders
Common: yawning.
Very rare: bronchospasm, nasal congestion, allergic alveolitis (pneumonia) with or without eosinophilia.
Skin and subcutaneous tissue disorders
Common: skin rash, urticarial.
Very rare: petechiae, itching, photosensitization (avoid excessive exposure to sunlight), alopecia.
Vascular disorders
Very common: hypotension, particularly orthostatic hypotension with associated vertigo.
Very rare: hypertension, peripheral vasospastic reactions.
Withdrawal Symptoms
Abrupt cessation of treatment with TCAs after prolonged administration may occasionally produce nausea, vomiting, abdominal pain, diarrhea, insomnia, nervousness, anxiety, headache and malaise. These symptoms are not indicative of addiction.
8.5 Post-Market Adverse Reactions
The following adverse drug reactions have been reported during post-approval use of clomipramine hydrochloride. Because this reaction is reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate frequency.
Central Nervous System: Cases of hyperthermia have been recorded by nondomestic post-marketing surveillance systems. Most cases occurred when clomipramine hydrochloride was used in combination with other drugs. When clomipramine hydrochloride and a neuroleptic were used concomitantly, the cases were sometimes considered to be examples of a neuroleptic malignant syndrome.
Endocrine Disorders – Syndrome of inappropriate antidiuretic hormone secretion (SIADH).
Eye Disorders – Angle-closure glaucoma.
Immune System Disorders – Drug Rash with Eosinophilia and Systemic Symptoms (DRESS).
Metabolism and Nutrition Disorders – Hyponatremia.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Metabolism of clomipramine
The primary route of clomipramine metabolism is demethylation to form the active metabolite, N-desmethylclomipramine, which can be formed by several P450 enzymes, primarily CYP3A4, CYP2C19 and CYP1A2.
Drugs Metabolized by P450 2D6 – The biochemical activity of the drug metabolizing isozyme cytochrome P450 2D6 (debrisoquin hydroxylase) is reduced in a subset of the Caucasian population (about 7% to 10% of Caucasians are so-called “poor metabolizers”); reliable estimates of the prevalence of reduced P450 2D6 isozyme activity among Asian, African and other populations are not yet available. Poor metabolizers have higher than expected plasma concentrations of tricyclic antidepressants (TCAs) when given usual doses. Depending on the fraction of drug metabolized by P450 2D6, the increase in plasma concentration may be small, or quite large (8- fold increase in plasma AUC of the TCA). In addition, certain drugs inhibit the activity of this isozyme and make normal metabolizers resemble poor metabolizers. An individual who is stable on a given dose of TCA may become abruptly toxic when given one of these inhibiting drugs as concomitant therapy. The drugs that inhibit cytochrome P450 2D6 include some that are not metabolized by the enzyme (quinidine; cimetidine) and many that are substrates for P450 2D6 (many other antidepressants, phenothiazines, and the Type 1C antiarrhythmics propafenone and flecainide). While all the selective serotonin reuptake inhibitors (SSRIs), e.g., fluoxetine, sertraline, paroxetine, and fluvoxamine, inhibit P450 2D6, they may vary in the extent of inhibition. Fluvoxamine has also been shown to inhibit P450 1A2, an isoform also involved in TCA metabolism. The extent to which SSRI-TCA interactions may pose clinical problems will depend on the degree of inhibition and the pharmacokinetics of the SSRI involved. Nevertheless, caution is indicated in the co-administration of TCAs with any of the SSRIs and also in switching from one class to the other. Of particular importance, sufficient time must elapse before initiating TCA treatment in a patient being withdrawn from fluoxetine, given the long half-life of the parent and active metabolite (at least 5 weeks may be necessary). Concomitant use of agents in the tricyclic antidepressant class (which includes TARO-CLOMIPRAMINE) with drugs that can inhibit cytochrome P450 2D6 may require lower doses than usually prescribed for either the tricyclic antidepressant agent or the other drug. Furthermore, whenever one of these drugs is withdrawn from co-therapy, an increased dose of tricyclic antidepressant agent may be required. It is desirable to monitor TCA plasma levels whenever an agent of the tricyclic antidepressant class including TARO-CLOMIPRAMINE is going to be co-administered with another drug known to be an inhibitor of P450 2D6 (and/or P450 1A2).
Because TARO-CLOMIPRAMINE is highly bound to serum protein, the administration of TARO-CLOMIPRAMINE to patients taking other drugs that are highly bound to protein (e.g., warfarin, digoxin) may cause an increase in plasma concentrations of these drugs, potentially resulting in adverse effects. Conversely, adverse effects may result from displacement of protein-bound TARO-CLOMIPRAMINE by other highly bound drugs.
9.3 Drug-Behavioural Interactions
Alcohol: Patients should be warned that, while taking TARO-CLOMIPRAMINE, their responses to alcoholic beverages may be exaggerated.
Smoking: Known inducers of CYP1A2 (e.g. nicotine/components in cigarette smoke) decrease plasma concentrations of tricyclic drugs. In cigarette smokers, clomipramine steady-state plasma concentrations were decreased 2-fold compared to non-smokers (no change in N-desmethylclomipramine).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug -Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Anticholinergics or Neuroleptics | T | Hyperexcitation states, delirium glaucoma | When TCAs are given in combination with anticholinergics or neuroleptics with an anticholinergic action, hyperexcitation states or delirium may occur, as well as attacks of glaucoma. |
| Antihypertensives | T | ↓ antihypertensive effects | Since TARO-CLOMIPRAMINE may diminish or abolish the antihypertensive effects of guanethidine, bethanidine, clonidine, reserpine, or alpha-methyldopa, patients requiring concomitant treatment for hypertension should be given antihypertensives of a different type (e.g., vasodilators, beta-blockers). |
Arrhythmic agents (quinidine type) | T | TCAs should not be employed in combination with anti-arrhythmic agents of the quinidine type (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular). |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Barbiturates, carbamazepine, phenytoin, and oral contraceptives | T | ↓ TARO-CLOMIPRAMINE | Substances which activate the hepatic mono-oxygenase enzyme system (e.g., barbiturates, carbamazepine, phenytoin, nicotine and oral contraceptives) may lower plasma concentrations of TCAs and so reduce their antidepressive effects. In addition, TARO-CLOMIPRAMINE may increase plasma levels of phenytoin and carbamazepine, therefore, it may be necessary to adjust the dosage of these drugs. |
| Buspirone | T | ↑ Risk for serotonin toxicity | Concomitant use of TCAs, such as clomipramine hydrochloride and buspirone may increase the risk of serotonin toxicity, a potentially life-threatening condition. See 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin Syndrome |
Cimetidine or Methylphenidate | C | ↑ TARO-CLOMIPRAMINE | Caution should be exercised if TARO-CLOMIPRAMINE is administered together with cimetidine or methylphenidate since these drugs have been shown to inhibit the metabolism of several TCAs. Clinically significant increases in plasma levels of TARO-CLOMIPRAMINE may occur, necessitating a dosage reduction. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| CNS depressants or Anticholinergic agents | T | ↑ TARO-CLOMIPRAMINE | Patients should be warned that, while taking TARO-CLOMIPRAMINE, their responses to CNS depressants (e.g., barbiturates, benzodiazepines or general anesthetics) or anticholinergic agents (e.g., atropine, antihistamines, biperiden, levodopa) may be exaggerated. Close supervision and careful adjustment of dosage are required when TARO-CLOMIPRAMINE is administered with anticholinergic drugs. |
| Coumarin drugs | T | ↑anticoagulant effect | TCAs may potentiate the anticoagulant effect of coumarin drugs by inhibiting hepatic metabolism of these drugs. Careful monitoring of plasma prothrombin is therefore advised. |
| Diuretics | T | Hypokalemia | Comedication with diuretics may lead to hypokalemia, which should be treated prior to administration of TARO-CLOMIPRAMINE. |
| Estrogens | T | ↑clomipramine | If administered concomitantly with estrogens, the dose of clomipramine should be reduced since steroid hormones inhibit the metabolism of clomipramine. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Fluoxetine, fluvoxamine and other selective serotonin reuptake inhibitors (SSRIs) | T | ↑ TARO-CLOMIPRAMINE ↑Risk for serotonin toxicity | Fluoxetine, fluvoxamine and other selective serotonin reuptake inhibitors (SSRIs) may increase the activity and plasma concentrations of TCAs, such as TARO-CLOMIPRAMINE, with corresponding adverse effects. Comedication with SSRIs may lead to additive effects on the serotonergic system. If concomitant treatment with TARO-CLOMIPRAMINE and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin Syndrome). |
| General anesthetics | T | TARO-CLOMIPRAMINE should be discontinued prior to elective surgery for as long as is clinically feasible, since little is known about the interaction with general anesthetics. | |
| Lithium | T | ↑ Risk for serotonin toxicity | Concomitant use of TCAs, such as clomipramine hydrochloride, and lithium may increase the risk of serotonin toxicity, a potentially life-threatening condition. |
| Noradrenaline or adrenaline, amphetamine, sympathomimetics | T | ↑cardiovascular effects | TARO-CLOMIPRAMINE may potentiate the Cardiovascular effects of noradrenaline or adrenaline, amphetamine, as well as nasal drops and local anesthetics containing sympathomimetics (e.g., isoprenaline, ephedrine, phenylephrine). |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Opioids (e.g. tramadol, fentanyl) | T | ↑Risk for serotonin toxicity ↑Risk for seizures and opioid toxicity with concomitant use of tramadol. | Concomitant use of TCAs, such as clomipramine hydrochloride and triptans may increase the risk of serotonin toxicity, a potentially life-threatening condition. See 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin Syndrome Concomitant use of TCAs, such as clomipramine and tramadol also increases the risk for seizures. In addition, this combination can inhibit the metabolism of tramadol to the active metabolite and thereby increasing tramadol concentrations, potentially causing opioid toxicity. |
| Phenobarbital | T | ↑Phenobarbital | Administration of TARO-CLOMIPRAMINE has been reported to increase the plasma levels of phenobarbital, if given concomitantly. |
| Phenothiazines, butyrophenones, thioridazine and diazepam | T | ↑ TARO-CLOMIPRAMINE | Concomitant treatment with neuroleptic agents (e.g., phenothiazines and butyrophenones) may result in increased plasma concentrations of TARO-CLOMIPRAMINE a lowered convulsion threshold and seizures. Combination with thioridazine may produce cardiac arrhythmias. No such effects are known to occur in combination with diazepam but it might be necessary to lower the dosage of TARO-CLOMIPRAMINE if administered concomitantly with alprazolam or disulfiram. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Triptans | T | ↑Risk for serotonin toxicity | Concomitant use of TCAs, such as clomipramine hydrochloride, and triptans may increase the risk of serotonin toxicity, a potentially life-threatening condition. See 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity / Serotonin Syndrome |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Interactions resulting in decreased effect of TARO-CLOMIPRAMINE
CYP3A and CYP2C inducers, such as rifampicin or anticonvulsants (e.g. barbiturates, carbamazepine, phenobarbital and phenytoin), may decrease clomipramine concentrations as concomitant administration of drugs known to induce cytochrome P450 enzymes, particularly CYP3A4, CYP2C19 may accelerate the metabolism and decrease the efficacy of TARO-CLOMIPRAMINE.
9.5 Drug-Food Interactions
Concomitant administration of TARO-CLOMIPRAMINE with grapefruit, grapefruit juice, or cranberry juice may increase the plasma concentrations of clomipramine. Caution is therefore required when prescribing TARO-CLOMIPRAMINE to patients taking these products.
9.6 Drug-Herb Interactions
Concomitant administration of St. John's Wort may reduce the plasma levels of clomipramine. Caution is therefore required when prescribing TARO-CLOMIPRAMINE to patients taking St. John's Wort.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
TARO-CLOMIPRAMINE (clomipramine hydrochloride) is a tricyclic agent with both antidepressant and antiobsessional properties. Like other tricyclics, clomipramine inhibits norepinephrine and serotonin uptake into central nerve terminals, possibly by blocking the membrane-pump of neurons. Clomipramine thereby increases the concentration of transmitter monoamines at receptor sites. Clomipramine is presumed to influence depression and obsessive and compulsive behavior through its effects on serotonergic neurotransmission. The actual neurochemical mechanism is unknown, but clomipramine’s capacity to inhibit serotonin reuptake is thought to be important. Clomipramine appears to have a mild sedative effect that may be helpful in alleviating the anxiety component often accompanying depression.
As with other tricyclic compounds, clomipramine hydrochloride possesses anticholinergic properties which are responsible for certain side effects. It also has weak antihistamine and antiserotoninergic properties, lowers the convulsive threshold, potentiates the effect of norepinephrine and other drugs acting on the central nervous system, has a quinidine-like effect on the heart and may impair cardiac conduction.
The action of TARO-CLOMIPRAMINE on the human electroencephalogram is one of desynchronization. Clomipramine causes a persistent increase in the frequency of shifts into stage I sleep and produces marked reduction or suppression of rapid eye movement sleep (REM or paradoxical sleep). Partial recovery occurs within 3 to 4 weeks as does a rebound after drug withdrawal which appears to last approximately the same time. In normal human volunteers tricyclic antidepressants (TCAs) tend to produce a sedative effect accompanied by atropine-like symptoms and may produce some difficulty in concentrating and thinking.
10.2 Pharmacodynamics
The pharmacological properties of clomipramine are similar to those of other TCAs, the main differences being quantitative rather than qualitative. The pharmacological profile of clomipramine includes reversal of reserpine and tetrabenazine effects, slight depressant effects on the central nervous system as manifested by behavioral, motor, electrocortical and visceral activity, anticholinergic and antihistaminic effects, and potentiation of adrenergic and serotonergic functions.
Clomipramine has a weak anticholinergic action demonstrated in laboratory animals by attenuation of the effect of acetylcholine on blood pressure and electrical stimulation of the vagus, and slight counteraction of pilocarpine-induced salivation. The ED50 for inhibition of tremorine-induced tremor in the mouse was 3.3 mg/kg. At 50 mg/kg, there was only incomplete inhibition of cholinergic intoxication due to tremorine (25 mg/kg I.P.). Clomipramine also has an antihistaminic effect demonstrated by inhibition of the fall in blood pressure following histamine injection in the cat.
As with other tricyclic agents, clomipramine produces a depression of spontaneous motor activity in laboratory animals (ED50 approximately 40 mg/kg I.P.). Clomipramine can also produce irritability and aggressiveness. Clomipramine was considerably less effective than amitriptyline in depressing locomotor activity and similar in effectiveness to imipramine. However, on the rotating cylinder and wire traction tests, clomipramine was almost inactive, while imipramine and amitriptyline were active at relatively high doses. As with imipramine, clomipramine demonstrated only slight cataleptic activity and potentiated slightly bulbocapnine catalepsy at 50 mg/kg. However, unlike imipramine and amitriptyline, it exhibited no anticataleptic activity in chlorpromazine-induced catalepsy at the same dosage. Clomipramine also exhibited antiserotonin action, but was about 2½ times less effective than chlorpromazine in protecting against serotonin contraction of the guinea pig ileum.
Clomipramine has a depressant effect on behavioral and electrocortical arousal. Unlike the neuroleptic agents, this effect is more pronounced on electrocortical activity than on behavior. Clomipramine is as active as amitriptyline in producing slow waves of high voltage in the EEG of rabbits and in blocking the reaction induced by stimulation of the mesencephalic reticular formation. In low doses (1.25 mg/kg), clomipramine increased the duration and amplitude of after-discharges evoked by stimulation of the amygdala and had no effect on the recruiting response induced by stimulation of the anteromedian thalamic nucleus. In cats, clomipramine was found to suppress 'fast sleep' with progressive recovery. Performance on several conditioned tests was not affected significantly by clomipramine, imipramine or amitriptyline at doses up to 20 mg/kg. At doses of 10 mg/kg, clomipramine and imipramine pressed responding during the acquisition period of a conditioned avoidance test. Clomipramine is significantly less effective in inhibiting aggressive behavior in fighting mice (ED50 28 mg/kg) than imipramine (ED50 10 mg/kg) or amitriptyline (ED50 8 mg/kg). Clomipramine exerts a partial protective action against electroshock and pentylenetetrazol-induced tonic seizures in the rat with no effect in doses up to 50 mg/kg against strychnine convulsions in the mouse. The drug appears to be devoid of analgesic activity and produced only a slight depression of respiration in the non-anesthetized rabbit.
Antiarrhythmic effects of clomipramine in the dog were similar, but of shorter duration than those resulting from the quinidine-like action also observed with imipramine. As with imipramine, low doses (below 3 mg/kg I.V.), caused myocardial stimulation; cardiac depression occurred at higher doses. Clomipramine and amitriptyline were more active than imipramine in increasing the duration of barbiturate sleep. Clomipramine also demonstrated anti-emetic activity in dogs at doses of 10 mg/kg S.C.
Clomipramine occupies an intermediate position in reversing reserpine and tetrabenazine- induced catalepsy and ptosis. The anticholinergic effect of the drug combined with the potentiation of catecholamines may account for counteraction of ptosis. As with other tricyclics, it potentiates sympathetic functions. Clomipramine was found to potentiate amphetamine-induced hyperthermia at 10 mg/kg S.C. and to block amphetamine toxicity in crowded mice at 75 mg/kg. It also potentiates the effect of adrenaline and noradrenaline on the blood pressure and the nictitating membrane of the anesthetized cat and inhibits the pressure effect of tyramine.
In histochemical and biochemical studies, clomipramine appeared more potent than imipramine in blocking serotonin uptake and in preventing 4-methyl-μ-ethyl-meta-tyramine induced depletion of serotonin in rat brain. Clomipramine was also more effective than amphetamine hyperthermia at 10 mg/kg S.C. and to block amphetamine toxicity in crowded mice at 75 mg/kg. It also potentiates the effect of adrenaline and noradrenaline on the blood pressure and the nictitating membrane of the anesthetizes cat and inhibits the pressure effect of tyramine.
Clomipramine was also more effective than imipramine in potentiating the effects of serotonin, tryptophan and nialamide on the extensor hind limb reflex in rats. Its effect on noradrenergic neurons was less pronounced.
10.3 Pharmacokinetics
Absorption
Clomipramine hydrochloride is rapidly and completely absorbed after oral administration in humans. Peak plasma levels are usually reached two hours after dosage, but much individual variation occurs. The plasma half-life after a single oral dose is approximately 21 hours. After 28 days of oral administration to patients in a daily dosage of 75 mg, plasma concentrations of clomipramine ranged from 17 to 70 ng/mL, (mean = 35.7 ng/mL). The concentration of the active metabolite, desmethylclomipramine, was about twice as high.
Distribution
The binding of clomipramine hydrochloride to serum proteins is very high at 96 to 97% and is practically concentration-independent within the therapeutic range. Clomipramine has a volume of distribution of approximately 12 L/kg.
Metabolism
Clomipramine is extensively metabolized in the body with hydroxylation, demethylation and N-oxidation being the quantitatively more important routes of metabolism.
Elimination
As expected, the metabolites of TARO-CLOMIPRAMINE are quite similar to those of imipramine, all retaining the benzazepine structure. Two-thirds of TARO-CLOMIPRAMINE is excreted as water-soluble conjugates in the urine and approximately one-third in the feces. After a 25 mg radiolabeled dose of clomipramine in 2 subjects, the urinary recoveries of clomipramine and desmethylclomipramine were about 2% and 0.5% of the total radioactivity, respectively.
Animal Pharmacokinetics
Clomipramine is rapidly absorbed after oral administration to rabbits and rats and distributes to several organs, particularly liver and lungs, without exceeding blood plasma concentrations of 0.1 %. While clomipramine and imipramine follow similar distribution patterns in the rat after oral administration, clomipramine remains in various organs of the rabbit longer than imipramine. In the rabbit, the pattern of the breakdown products of clomipramine differs from imipramine, clomipramine giving rise to fewer conjugated metabolites. Clomipramine and imipramine are both catabolized via demethylation, hydroxylation of the ring structure, N-oxidation and removal of the side chain. In rabbit urine, only about 2% of the amount administered was found (by chromatography) unchanged.
Special Populations and Conditions
- Pediatrics (< 18 years of age): Health Canada has not authorized an indication for use in depression in pediatric patients (see 1.1 Pediatrics).
- Pediatrics (<10 years): Health Canada has not authorized an indication for pediatric use in obsessive compulsive disorder (OCD) in children under 10 years of age.
- Pediatrics (10 to 17 years of age): Limited information is available for the use of TARO-CLOMIPRAMINE for OCD in children aged 10 to 17 years, therefore, TARO-CLOMIPRAMINE is not recommended for use in this population. The long-term effects of TARO-CLOMIPRAMINE on childhood growth and development have not been determined.
- Geriatrics: Owing to the lower clearance of clomipramine in plasma, elderly patients require lower doses of TARO-CLOMIPRAMINE than patients in younger age groups.
- Pregnancy and Breast-feeding: Clomipramine passes into breast milk, TARO-CLOMIPRAMINE should be gradually withdrawn or the infant weaned if the patient is breast-feeding.
- Genetic Polymorphism: TCAs including clomipramine are primarily metabolised by the hepatic cytochrome P450 isozymes CYP2D6 and CYP2C19, which are polymorphic in the population. Patients known to be poor CYP2D6 or CYP2C19 metabolisers may have higher plasma levels of clomipramine (see 9.2 Drug Interactions Overview). Dosage adjustments should be considered (see 4.2 Recommended Dose and Dosage Adjustment, Concomitant use with inhibitors of cytochrome P450 enzymes; CYP3A and CYP2C inducers).
11 STORAGE, STABILITY AND DISPOSAL
Protect from heat (store between 15°C and 30°C).
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
None
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Clomipramine hydrochloride
Chemical Name: 3 -chloro-5 - [3 - (dimethylamino)propyl]- 10, 11 -dihydro-5H-dibenz [b, f] azepine monohydrochloride
Molecular Formula and Molecular Mass: C19H23ClN2 • HCl and 351.3 g/mol
Structural formula:
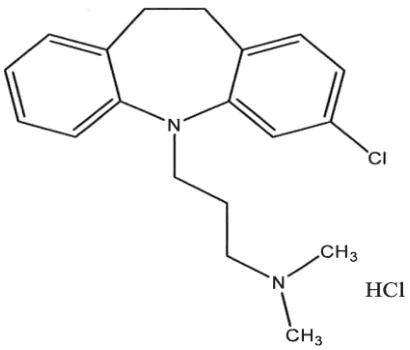
Physicochemical properties: White or slightly yellow crystalline powder, slightly hygroscopic. Freely soluble in water and dichloromethane, soluble in ethanol (96%). Practically insoluble in ether. With a pKa of 5.8 and 9.3 and a melting point of ca. 191 to 193oC.
14 CLINICAL TRIALS
14.3 Comparative Bioavailability Studies
50 mg tablets:
A double-blinded, randomized, single dose, two-way, cross-over, comparative bioavailability study of TARO-CLOMIPRAMINE 50 mg capsules (Taro Pharmaceuticals Inc.) and PrANAFRANIL® 50 mg tablets (Aspri Pharma Canada Inc.) was conducted in 44 healthy, adult male subjects under fasting conditions. Comparative bioavailability data from 37 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clomipramine (1 x 50 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72h 3 (ng·h/mL) | 694.9 754.5 (42.1) | 678.6 761.7 (48.2) | 102.4 | 96.0 – 109.3 |
AUCI 3 (ng·h/mL) | 858.1 963.7 (50.8) | 853.0 1003.8 (58.8) | 100.6 | 93.3 – 108.5 |
Cmax (ng/mL) | 34.9 36.1 (38.1) | 34.7 37.7 (40.1) | 100.7 | 93.7 – 108.3 |
Tmax 4 (h) | 4.50 (2.00 – 7.50) | 4.50 (2.00 – 8.00) | ||
T½ 3,5 (h) | 34.16 (37.7) | 37.68 (38.9) | ||
1 TARO-CLOMIPRAMINE (clomipramine hydrochloride) capsules, 50 mg (Taro Pharmaceuticals Inc.)
2 PrANAFRANIL® (clomipramine hydrochloride) tablets, 50 mg (Aspri Pharma Canada Inc.)
3 n = 34 subjects
4 Expressed as the median (range) only
5 Expressed as arithmetic mean (CV %) only
25 mg tablets:
A double-blinded, randomized, single dose, two-way, cross-over, comparative bioavailability study of TARO-CLOMIPRAMINE 25 mg capsules (Taro Pharmaceuticals Inc.) and PrANAFRANIL® 25 mg tablets (AA Pharma Inc.) was conducted in 44 healthy, adult male subjects under fasting conditions. Comparative bioavailability data from 40 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clomipramine (1 x 25 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72h 3 (ng·h/mL) | 347.9 382.9 (44.2) | 343.2 373.2 (40.5) | 101.3 | 95.3 – 107.6 |
AUCI 3 (ng·h/mL) | 415.9 465.6 (46.8) | 415.9 471.1 (53.4) | 99.9 | 92.9 – 107.5 |
Cmax (ng/mL) | 17.3 19.2 (48.1) | 17.6 19.4 (43.9) | 98.1 | 93.1 – 103.5 |
Tmax4 (h) | 3.83 (1.50 – 8.00) | 3.67 (2.00 – 8.00) | ||
T½ 3,5 (h) | 31.0 (32.4) | 32.9 (43.0) | ||
1 TARO-CLOMIPRAMINE (clomipramine hydrochloride) capsules, 25 mg (Taro Pharmaceuticals Inc.)
2 PrANAFRANIL® (clomipramine hydrochloride) tablets, 25 mg (AA Pharma Inc., Canada)
3 n = 39 subjects
4 Expressed as the median (range) only
5 Expressed as arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
The acute toxicity of clomipramine administered by oral, subcutaneous, intravenous and intraperitoneal routes has been studied in the mouse, rat, guinea pig, rabbit, and dog. Equal numbers of male and female animals were used and, in the case of mouse and rat, the number of animals per dose was ten. Clomipramine was given orally in a gum arabic suspension and, by the other routes, in aqueous solution. The animals were observed for a period of 8 days. The LD50 for each route of administration was determined by the method of Litchfield-Wilcoxon. Toxic manifestations included drowsiness, ventrolateral position, respiratory disturbances, ataxia and tonic-clonic convulsions.
Table 3 - Acute LD50 Values for Clomipramine
| Species | Route | LD50 mg/kg |
|---|---|---|
| Mouse | P.O. S.C. I.V. I.P. | 630 245 44 98 |
| Rat | P.O. S.C. I.V. I.P. | 1450 1000 26 102 |
| Guinea Pig | P.O. I.V. | 575 30 |
| Rabbit | P.O. I.V. | 700 17 |
| Dog | I.V. | 40 |
Chronic Toxicity
One-year toxicity studies were performed on rats and dogs.
Rat
Doses of 0, 12.5, 25, 50 and 100 mg/kg of clomipramine were administered daily to Sprague Dawley rats (thirty-five males and thirty-five females per group). There was an increase in spontaneous mortality in animals in the highest dosage group only. No clinical or pathological alterations were noticed, except that histological examination revealed disturbance of spermatogenesis in male rats at higher dosages.
Dog
Doses of 0, 12.5, 50 and 100 mg/kg of clomipramine were administered daily to pedigree Pembrokeshire Corgi dogs (four males and four females per group). Spontaneous death occurred only in the highest dosage group. Clinical and pathological studies, autopsy findings and measurement of organ weight gave no indication of a toxic effect of clomipramine, except that testicular damage was again apparent at higher doses.
One dog in the high dose group (100 mg/kg/day) showed no evidence of any mature spermatozoa. Spermatogenesis in this animal did not appear to extend beyond the secondary spermatocyte or spermatid stage. The histological picture did not suggest immaturity. In 2 of the intermediate dose level animals (50 mg/kg/day) there was evidence of bilateral inhibition of spermatogenesis associated with atrophy of some of the cells of the seminiferous tubules. In one dog (50 mg/kg/day), there is a possibility of some reduction in cellularity of some of the seminiferous tubules, although mature cell forms were present in this animal. The testes of low dose (12.5 mg/kg/day) and control animals were within normal limits and active spermatogenesis with mature cell forms was seen.
A 29-day intramuscular toxicity study was also performed in Beagle dogs. The dogs received doses of 0, 1 or 2 mg/kg clomipramine (two males and two females per group). No significant clinical or pathological changes were observed.
Other Chronic Toxicity Studies
As with other tricyclic compounds, TARO-CLOMIPRAMINE has been associated with changes in testicular and lung tissue in long-term animal toxicology studies. In 1 and 2 year studies in rats, a dose 4 times the maximum daily human dose was associated with phospholipidosis in the lungs and changes in the testes (atrophy, aspermatogenesis, and calcification). In a 1 year toxicity study in dogs, testicular atrophy was detected in animals receiving 10 times the maximum recommended daily human dose.
Genotoxicity:
No studies have been performed to evaluate the mutagenic potential of clomipramine hydrochloride.
Carcinogenicity:
No animal studies have been performed to evaluate carcinogenic potential of clomipramine hydrochloride.
Reproductive and Developmental Toxicology:
Teratogenicity
Tests of the teratogenic effect of clomipramine were performed on Swiss White Mice, Wistar Rats, and a strain of New Zealand White Rabbits, known to be susceptible to the teratogenic effect of thalidomide.
At doses of 0, 15, 30 and 60 mg/kg/day in rabbits and 0, 12.5, 25, 50 and 100 mg/kg/day in rats and mice, there was no evidence to suggest that clomipramine produced fetal abnormality. Doses of 12 and 24 mg/kg/day administered to male rats for two months and to female rats for 2 weeks before mating caused only a reduction of male activity.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. ANAFRANIL, (tablets, 10 mg, 25 mg and 50 mg), Submission control 255249, product monograph, January 18, 2022
- 2. ANAFRANIL, (tablets, 10 mg, 25 mg and 50 mg), Submission control 268209, product monograph, MAY 02, 2023