


Product Monograph - Teva-Amitriptyline
ACTIONS AND CLINICAL PHARMACOLOGY
Amitriptyline hydrochloride is a tricyclic antidepressant with sedative properties. Its mechanism of action in man is not known. Amitriptyline inhibits the membrane pump mechanism responsible for the re-uptake of transmitter amines, such as norepinephrine and serotonin, thereby increasing their concentration at the synaptic clefts of the brain. Amitriptyline has pronounced anticholinergic properties and produces EKG changes and quinidine-like effects on the heart (See ADVERSE REACTIONS). It also lowers the convulsive threshold and causes alterations in EEG and sleep patterns.
Orally administered amitriptyline is readily absorbed and rapidly metabolized. Steady-state plasma concentrations vary widely and this variation may be genetically determined.
Amitriptyline is primarily excreted in the urine, mostly in the form of metabolites, with some excretion also occurring in the feces.
INDICATIONS AND CLINICAL USE
TEVA-AMITRIPTYLINE (amitriptyline hydrochloride) is indicated in the drug management of depressive illness.
TEVA-AMITRIPTYLINE may be used in depressive illness of psychotic or endogenous nature and in selected patients with neurotic depression. Endogenous depression is more likely to be alleviated than are other depressive states. TEVA-AMITRIPTYLINE, because of its sedative action, is also of value in alleviating the anxiety component of depression.
As with other tricyclic antidepressants, TEVA-AMITRIPTYLINE may precipitate hypomanic episodes in patients with bipolar depression. These drugs are not indicated in mild depressive states and depressive reactions.
CONTRAINDICATIONS
| TEVA-AMITRIPTYLINE (amitriptyline hydrochloride) is contraindicated in: | ||
| ||
| formulation (see PHARMACEUTCIAL INFORMATION, Composition) or component of the | ||
| container. | ||
| ||
| ||
| Amitriptyline should not be used in combination with a monoamine oxidase inhibitor (MAOI) due to the | ||
| risk of serotonin syndrome (a combination of symptoms that may include agitation, | ||
| confusion, tremor, myoclonus, and hyperthermia). Hyperpyretic crises, severe convulsions, and | ||
| deaths have occurred in patients receiving concomitant tricyclic, antidepressants and MAOIs. | ||
| Treatment with a MAOI should be discontinued at least 14 days before initiating treatment with | ||
| amitriptyline. Similarly, amitriptyline treatment should be discontinued at least 14 days before starting a | ||
| MAOI (see DOSAGE AND ADMINISTRATION). | ||
WARNINGS
| Amitriptyline should be used with caution in patients with a history of seizures, impaired liver function or | ||
| blood dyscrasias. Due to its anticholinergic activity, amitriptyline should be used with caution in patients | ||
| with a history of urinary retention, or with narrow-angle glaucoma or increased intraocular pressure. | ||
| As with other antidepressants, TEVA-AMITRIPTYLINE can cause mydriasis, which may trigger an angle- | ||
| closure attack in a patient with anatomically narrow ocular angles (see ADVERSE REACTIONS). | ||
| Healthcare providers should inform patients to seek immediate medical assistance if they experience eye | ||
| pain, changes in vision or swelling or redness in or around the eye. In patients with narrow-angle glaucoma, | ||
| even average doses may precipitate an attack. | ||
| Patients with cardiovascular disorders should be closely monitored. Tricyclic antidepressant drugs, | ||
| including amitriptyline have been reported to produce arrhythmias, sinus tachycardia, prolongation of the | ||
| conduction time and severe hypotension, particularly at high doses. Myocardial infarction and stroke have | ||
| been reported with drugs of this class (see ADVERSE REACTIONS). Cardiac arrhythmias and severe | ||
| hypotension may also occur at normal doses in patients with pre-existing cardiovascular disease. A few | ||
| instances of unexpected death have been reported in patients with cardiovascular disorders. Therefore, these | ||
| drugs should be used with caution in patients with a history of cardiovascular disease, such as myocardial | ||
| infarction, congestive heart failure (see CONTRAINDICATIONS) and conduction abnormalities. | ||
| There has been a report of fatal dysrhythmia occurring as late as 56 hours after amitriptyline overdose. | ||
| Caution is recommended when amitriptyline is administered to hyperthyroid patients or those receiving | ||
| thyroid medication. Cardiac arrhythmias may develop when tricyclic antidepressants are used | ||
| concomitantly with thyroid medications. | ||
| QT interval prolongation | ||
| Cases of QT interval prolongation and arrhythmia have been reported during the post-marketing | ||
| period (see ADVERSE REACTIONS, Cardiovascular). Caution is advised in patients with significant | ||
| bradycardia, in patients with uncompensated heart failure, or in patients concurrently taking QT-prolonging | ||
| drugs (see PRECAUTIONS, Drug Interactions). Electrolyte disturbances (hypokalaemia, hyperkalaemia, | ||
| hypomagnesaemia) are also known to increase the proarrythmic risk. | ||
| Concurrent administration of amitriptyline and electroconvulsive therapy may increase the hazards of | ||
| therapy. Such treatment should be limited to patients for whom it is essential. | ||
| Amitriptyline may impair mental and/or physical abilities required for the performance of hazardous tasks, | ||
| such as operating machinery or driving a motor vehicle. Patients should be advised to avoid such tasks until | ||
| they know how amitriptyline affects them. |
Fertility: Amitriptyline reduced the pregnancy rate in rats. No data on the effects of amitriptyline on human fertility are available.
Pregnant Women::
There are no adequate and well-controlled studies in pregnant women. When considering treatment with amitriptyline in pregnant women or women who may become
pregnant, the potential benefits must be weighed against the possible hazards to mother and child. Amitriptyline is not recommended during pregnancy unless clearly necessary and only after careful consideration of the risk/benefit.
Nursing Women: Amitriptyline and its metabolites are excreted in breast milk. Because of the potential for serious adverse reactions in infants from amitriptyline, a decision should be made whether to discontinue nursing or discontinue the drug.
Pediatrics:
The safety and efficacy of amitriptyline have not been established in patients under 12 years of age. The use of amitriptyline in pediatric patients is not recommended (see DOSAGE and ADMINISTRATION).
Geriatrics (> 65 years of age): Geriatric patients are particularly sensitive to the anticholinergic side effects of tricyclic antidepressants including amitriptyline hydrochloride. Peripheral anticholinergic effects include tachycardia, urinary retention, constipation, dry mouth, blurred vision, and exacerbation of narrow angle glaucoma. Central nervous system anticholinergic effects include cognitive impairment, psychomotor slowing, confusion, sedation, and delirium.
Elderly patients taking amitriptyline hydrochloride may be at increased risk for falls.
Elderly patients should be started on low doses of amitriptyline and observed closely due to the greater frequency of decreased hepatic function, concomitant disease and other drug therapy in elderly patients (see DOSAGE AND ADMINISTRATION).
PRECAUTIONS
The potency of amitriptyline is such that addition of other antidepressant drugs generally does not result in any additional therapeutic benefit. Untoward reactions have been reported after the combined use of antidepressant agents having varying modes of activity. Accordingly, combined use of amitriptyline and other antidepressant drugs should be undertaken only with due recognition of the possibility of potentiation and with a thorough knowledge of the pharmacology of both drugs. There have been no reports of untoward events when patients receiving amitriptyline were changed immediately to protriptyline or vice versa.
When amitriptyline is used to treat the depressive component of schizophrenia, activation or exacerbation of existing psychotic manifestation may occur. Likewise, patients with bipolar disorder may experience hypomanic or manic episodes and hyperactive or agitated patients may become overstimulated when treated with amitriptyline. Paranoid delusions, with or without associated hostility, may be exaggerated. A reduction in dose or discontinuation of amitriptyline may be indicated and administration of a neuroleptic such as a phenothiazine, be considered under these circumstances.
The possibility of suicide is inherent in depression and remains during treatment High risk patients should be closely supervised throughout treatment. To minimize the risk of intentional overdose, prescriptions for TEVA-AMITRIPTYLINE should be written for the smallest possible quantity consistent with good patient management.
Discontinue the drug several days before elective surgery if possible.
Both elevation and lowering of blood glucose levels have been reported.
Drug Interactions:
Monoamine Oxidase Inhibitors: See CONTRAINDICATIONS
Tricyclic antidepressants may potentiate the cardiovascular effects of sympathomimetic drugs. Close supervision and careful adjustment of dosage are required when amitriptyline is administered with sympathomimetic drugs, including epinephrine combined with local anesthetics.
Tricyclic antidepressants may potentiate the effects of anticholinergic drugs on the eye, central nervous system, bowel and bladder and close supervision and careful adjustment of dosage are required. Paralytic ileus, urinary retention or acute glaucoma may occur in patients taking tricyclic antidepressants in combination with anticholinergic-type drugs, particularly in elderly or hospitalized patients.
Hyperpyrexia has been reported when tricyclic antidepressants are administered with anticholinergic agents or with neuroleptic drugs, particularly during hot weather.
Tricyclic antidepressants may counteract the antihypertensive effects of centrally acting antihypertensives such as clonidine and methyldopa. It is advisable to review all antihypertensive therapy during treatment with tricyclic antidepressants.
Cimetidine is reported to reduce hepatic metabolism of certain tricyclic antidepressants.
Amitriptyline may enhance the response to alcohol and the effects of barbiturates and other CNS depressants.
Delirium has been reported with concurrent administration of amitriptyline and disulfiram.
Drugs Metabolized by P450 2D6
The biochemical activity of the drug metabolizing isozyme cytochrome P450 2D6 (CYP 2D6) is reduced in a subset of the Caucasian population (about 7% to 10% of Caucasians are so called “poor metabolizers”); reliable estimates of the prevalence of reduced P450 2D6 isozyme activity among Asian, African, and other populations are not yet available. Poor metabolizers have higher than expected plasma concentrations of tricyclic antidepressants (TCAs) when given usual doses. Depending on the fraction of drug metabolized by CYP 2D6, the increase in plasma concentration may be small, or quite large (8-fold increase in plasma AUC of the TCA).
In addition, certain drugs that inhibit the activity of CYP 2D6 make normal metabolizers resemble poor metabolizers. An individual who is stable on a given dose of TCA may become abruptly toxic when given a drug that inhibits CYP 2D6 as concomitant therapy. The drugs that inhibit cytochrome P450 2D6 include some that are not metabolized by the enzyme (quinidine; cimetidine) and many that are substrates for CYP 2D6 (many other antidepressants, phenothiazines, and the Type 1C antiarrhythmics propafenone and flecainide). While selective serotonin reuptake inhibitors (SSRIs), e.g., fluoxetine, sertraline, and paroxetine, inhibit CYP 2D6, they may vary in the extent of inhibition. The extent to which SSRI-TCA interactions may pose clinical problems will depend on the degree of inhibition and the pharmacokinetics of the SSRI involved. Nevertheless, caution is indicated in the coadministration of TCAs with any of the SSRIs and also in switching from one class to the other. Of particular importance, sufficient time must elapse before initiating TCA treatment in a patient being withdrawn from fluoxetine, given the long half-life of the parent and active metabolite (at least 5 weeks may be necessary).
Concomitant use of tricyclic antidepressants with drugs that can inhibit cytochrome CYP 2D6 may require lower doses than usually prescribed for either the tricyclic antidepressant or the other drug. Furthermore, whenever one of these other drugs is withdrawn from cotherapy, an increased dose of tricyclic antidepressant may be required. Monitor TCA plasma levels whenever a TCA is going to be coadministered with another drug known to be an inhibitor of CYP 2D6.
Drugs which prolong the QT-interval including antiarrhythmics (e.g., quinidine, sotalol, disopyramide, amiodarone, some antipsychotics (e.g., pimozide, haloperidol), antidepressants (e.g., fluoxetine, tricyclic/tetracyclic antidepressants); macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, tacrolimus); quinolone antibiotics (e.g., ciprofloxacin); antimalarials (e.g., quinine, chloroquine); azole antifungals (e.g., ketoconazole); domperidone; 5-HT3 receptor antagonists (e.g., ondansetron); tyrosine kinase inhibitors (e.g., sunitinib); histone deacetylase inhibitors (e.g., vorinostat); and, beta-2 adrenoceptor agonists (e.g., salmeterol) may increase the likelihood of ventricular arrhythmias when taken with tricyclic antidepressants.
Use caution when using amitriptyline and methadone concomitantly due to a potential for additive effects on the QT interval and increased risk of serious cardiovascular effects.
Caution is also advised for co-administration of amitriptyline and diuretics inducing hypokalaemia (e.g. furosemide) (see WARNINGS, QT Interval Prolongation).
ADVERSE REACTIONS
Note: Included in the listing which follows are a few adverse reactions which have not been reported with this specific drug. However, pharmacological similarities among the tricyclic antidepressant drugs require that each of the reactions be considered when amitriptyline is administered.
Psychiatric: drowsiness, fatigue, activation of latent schizophrenia, disorientation, confusional states, hallucinations, delusions, hypomanic reactions, disturbed concentration, nightmares, insomnia, restlessness, agitation, excitement, jitteriness, anxiety, giddiness.
Neurologic: epileptiform seizures, coma, dizziness, tremors, numbness, tingling, parasthesias of the extremities, peripheral neuropathy, headache, ataxia, alteration in EEG patterns, extrapyramidal symptoms including abnormal involuntary movements and tardive dyskinesia, dysarthria, tinnitus, incoordination, and slurred speech.
Anticholinergic: urinary retention, dilatation of the urinary tract, constipation, paralytic ileus, especially in the elderly, hyperpyrexia, dry mouth, blurred vision, disturbance of accommodation, increased intraocular pressure, precipitation of latent glaucoma, aggravation of existing glaucoma, and mydriasis. Amitriptyline hydrochloride tablets can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of angle-closure glaucoma.
Cardiovascular: myocardial infarction, stroke, non-specific ECG changes and changes in AV conduction, prolonged conduction time, asystole, hypotension, syncope, hypertension, palpitation, QT interval prolongation, arrhythmias, heart block, ventricular tachycardia, fibrillation, unexpected death in patients with cardiovascular disorders.
Hematologic: bone marrow depression, including agranulocytosis, leukopenia, eosinophilia, purpura, thrombocytopenia.
Allergic: skin rash, urticaria, photosensitization, edema of the face and tongue, itching.
Gastrointestinal: nausea, epigastric distress, heartburn, vomiting, hepatitis (including altered liver function and jaundice), anorexia, stomatitis, peculiar taste, diarrhea, parotid swelling, black tongue.
Endocrine: testicular swelling, gynecomastia and impotence in the male, breast enlargement and galactorrhea in the female, increased or decreased libido, elevation and lowering of blood sugar levels, syndrome of inappropriate ADH (antidiuretic hormone) secretion.
Miscellaneous: weakness, increased perspiration, edema, urinary frequency, alopecia, increased appetite, weight gain, weight loss.
Withdrawal Symptoms: Abrupt cessation of treatment after prolonged administration may produce nausea, headache and malaise. Gradual dosage reduction has been reported to produce, within 2 weeks, transient symptoms including irritability, restlessness, and dream and sleep disturbance. These symptoms are not indicative of addiction. Rare instances have been reported of mania or hypomania occurring within 2 to 7 days following cessation of chronic therapy with tricyclic antidepressants.
Other reported adverse reactions for which a relationship could not be established include lupus-like syndrome (migratory arthritis, positive ANA and rheumatoid factor), hepatic failure and ageusia.
Post-market Adverse Events
A syndrome resembling neuroleptic malignant syndrome (NMS) has been very rarely reported after starting or increasing the dose of amitriptyline, with and without concomitant medications known to cause NMS. Symptoms have included muscle rigidity, fever, mental status changes, diaphoresis, tachycardia, and tremor.
Very rare cases of serotonin syndrome have been reported with amitriptyline in combination with other drugs that have a recognized association with serotonin syndrome.
Very rare cases of cardiomyopathy have been reported with amitriptyline.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
SYMPTOMS
| High doses may cause temporary confusion, disturbed concentration, or transient visual hallucinations. | ||
| Overdosage may cause drowsiness, hypothermia, tachycardia and other arrhythmic abnormalities, such as | ||
| bundle branch block, ECG evidence of impaired conduction, congestive heart failure, disorders of ocular | ||
| motility, convulsions, severe hypotension, stupor, coma, polyradiculoneuropathy and constipation. Other | ||
| symptoms may be agitation, hyperactive reflexes, muscle rigidity, vomiting, hyperpyrexia, or any of those | ||
| listed under ADVERSE REACTIONS. Symptoms of overdose may vary in severity depending on various | ||
| factors such as the amount of drug absorbed, the interval between drug ingestion and start of treatment, and | ||
| the age of the patient. In patients with glaucoma, even average doses may precipitate an attack. | ||
| TREATMENT | ||
| For the most current information for management of a suspected overdose, contact your | ||
| regional Poison Control Centre immediately. | ||
| Signs and symptoms of toxicity develop rapidly after tricyclic antidepressant overdose; therefore, hospital | ||
| monitoring is required as soon as possible. | ||
| In managing overdose, consider the possibility of multiple drug overdose, interactions among drugs, and | ||
| unusual drug kinetics. | ||
| Treatment is symptomatic and supportive. Cardiac arrhythmias and CNS involvement pose the greatest | ||
| threat and may occur suddenly even when initial symptoms appear to be mild. Therefore, patients who may | ||
| have ingested an overdosage of amitriptyline, particularly children, should be hospitalized and kept under | ||
| close surveillance. | ||
General
Obtain an ECG and immediately initiate cardiac monitoring. Protect the patient’s airway, establish an intravenous line and initiate gastric decontamination. A minimum of six hours of observation with cardiac monitoring and observation for signs of CNS or respiratory depression, hypotension, cardiac dysrhythmias and/or conduction blocks, and seizures is necessary. If signs of toxicity occur at any time during the period, extended monitoring is required. There are case reports of patients succumbing to fatal dysrhythmias late after overdose (see WARNINGS); these patients had clinical evidence of significant poisoning prior to death and most received inadequate gastrointestinal decontamination. Monitoring of plasma drug levels should not guide management of the patient.
Gastrointestinal Decontamination
EMESIS IS CONTRAINDICATED. All patients suspected of tricyclic antidepressant overdose should receive gastrointestinal decontamination. This should include, large volume gastric lavage followed by activated charcoal. If consciousness is impaired, the airway should be secured prior to lavage.
Cardiovascular
A maximal limb lead QRS duration of ≥ 0.10 seconds may be the best indication of the severity of the overdose. Intravenous sodium bicarbonate should be used to maintain the serum pH in the range of 7.45 to 7.55. If the pH response is inadequate, hyperventilation may also be used. Concomitant use of hyperventilation and sodium bicarbonate should be done with extreme caution, with frequent pH monitoring. A pH > 7.60 or a pCO < 20 mm Hg is undesirable. Dysrhythmias unresponsive to sodium bicarbonate therapy/hyperventilation may respond to lidocaine or bretylium. Type 1A and 1C antiarrhythmics are generally contraindicated (e.g., quinidine, disopyramide and procainamide and flecainide).
In rare instances, hemoperfusion may be beneficial in acute refractory cardiovascular instability in patients with acute toxicity. However, hemodialysis, peritoneal dialysis, exchange transfusions, and forced diuresis generally have been reported as ineffective in tricyclic antidepressant poisoning.
CNS
In patients with CNS depression early intubation is advised because of the potential for abrupt deterioration. Seizures should be controlled with benzodiazepines, or if these are ineffective, other anticonvulsants (e.g., phenobarbital, phenytoin).
DOSAGE AND ADMINISTRATION
Dosage should be initiated at a low level and increased gradually, noting carefully the clinical response and any evidence of intolerance.
Outpatient Adults: The recommended initial dose for ambulatory patients is 25 mg 3 times a day. Depending upon tolerance and response, this may be increased to a total of 150 mg a day.
Increases are made preferably in the late afternoon and/or bedtime doses. The sedative effect is usually rapidly apparent. The antidepressant activity may be evident within 3 or 4 days or may take up to 30 days to develop adequately.
Hospitalized Patients: Severely ill or hospitalized patients may require 100 mg a day initially. This can be increased gradually to 200 mg a day if necessary. A small number of hospitalized patients may need as much as 300 mg a day.
Pediatric Patients: The use of amitriptyline in pediatric patients is not recommended (see WARNINGS, Pediatrics).
Adolescent and Elderly Patients: When considering the use of amitriptyline in adolescent or elderly patients, the potential risks must be balanced with clinical need (see WARNINGS). In general, lower dosages are recommended for these patients. In those patients who may not tolerate higher doses, 50 mg daily may be satisfactory. The dose may be administered in divided doses or as a single dose preferably in the evening or at bedtime.
Maintenance: When satisfactory improvement has been reached, dosage should be reduced to the lowest amount that will maintain relief of symptoms. The usual maintenance dose is 50 to 100 mg/day in divided doses; however, in suitable patients, the total daily dosage may be given in a single dose, preferably at bedtime. It is appropriate to continue maintenance therapy throughout the active phase of the depression and for the expected duration of the depressive episode, in order to minimize the possibility of relapse.
Plasma Levels: Because of the wide variation in the absorption and distribution of tricyclic antidepressants in body fluids, it is difficult to directly correlate plasma levels and therapeutic effect. However, determination of plasma levels may be useful in identifying patients who appear to have toxic effects and may have excessively high levels, or those in whom lack of absorption or non-compliance is suspected. Adjustments in dosage should be made according to the patient's clinical response and not on the basis of plasma levels.
AVAILABILITY
TEVA-AMITRIPTYLINE tablets are available in film-coated tablets as the following:
10 mg amitriptyline hydrochloride as blue, circular biconvex, film-coated tablets having an embossing of ‘rph’ on one side and ‘A114’ on the other side. Available in bottles of 100 and 1000.
25 mg amitriptyline hydrochloride as yellow, circular biconvex, film-coated tablets having an embossing of ‘rph’ on one side and ‘A113’ on the other side. Available in bottles of 100 and 1000.
50 mg amitriptyline hydrochloride as beige, circular biconvex, film-coated tablets having an embossing of ‘rph’ on one side and ‘A112’ on the other side. Available in bottles of 100 and 1000.
COMPOSITION
TEVA-AMITRIPTYLINE (amitriptyline hydrochloride USP) tablets are available in 3 strengths containing 10 mg, 25 mg, and 50 mg amitriptyline per tablet.
The following non-medicinal ingredients are common to all tablet strengths:
colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, pregelatinised starch.
Coating ingredients are present in the tablets as follows:
10 mg: Hypromellose, Titanium Dioxide, Triacetin, FD&C Blue #1 Aluminum Lake, FD&C Yellow # 6
Aluminum Lake
25 mg: Hypromellose, Titanium Dioxide, Triacetin, D&C Yellow #10 Aluminum Lake, FD&C Blue #1
Aluminum Lake, FD&C Yellow # 6 Aluminum Lake
50 mg: Polyvinyl Alcohol, Titanium Dioxide, Polyethylene Glycol, Talc, Black Iron Oxide, Iron Oxide
Red, Yellow Iron Oxide.
STORAGE
Store at room temperature (15-30°C). Keep in a tightly closed container. Protect from moisture.
CHEMISTRY AND PHARMACOLOGY
A two-way crossover, blinded, single-dose, fasting, bioequivalence study of amitriptyline 50 mg tablets versus Apo®-amitriptyline 50 mg tablets in 23 normal, healthy, non-smoking male subjects was conducted. The summary of results is in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Amitriptyline (1 x 50 mg) From measured data uncorrected for potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 607.7 662.8 (41.5) | 571.0 648.6 (46.4) | 106.4 | 99.78 – 113.5 |
AUCI (ng·h/mL) | 684.7 752.5 (42.4) | 647.1 744.0 (47.9) | 105.8 | 99.20 – 112.9 |
Cmax (ng/mL) | 33.32 35.50 (37.01) | 32.15 35.63 (43.68) | 103.6 | 94.98 – 113.1 |
Tmax§ (h) | 4.22 (39.62) | 4.46 (42.64) | ||
T½§ (h) | 23.60 (16.86) | 23.71 (21.66) | ||
* Amitriptyline Hydrochloride Tablets USP 50 mg (Teva Canada Limited, formally ratiopharm inc. Canada) purchased in Canada
† Apo-Amitriptyline (Amitriptyline Hydrochloride Tablets USP) 50 mg (Apotex, Canada) § Expressed as median (range) only
Amitriptyline hydrochloride is 3-[10,11-dihydro-5H-dibenzo(a,d)-eyclohepten-5-ylidene]-N,N-dimethyl-1-propanamine hydrochloride, and has the following structural formula: 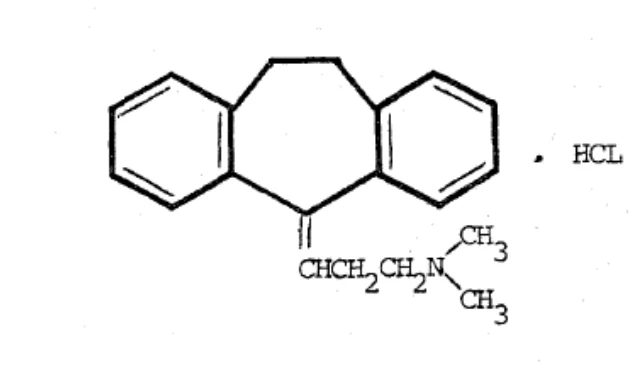
Amitriptyline has qualitatively similar pharmacologic actions to other tricyclic antidepressants in experimental animals. It is more sedative than imipramine, reducing spontaneous motor activity at lower doses. It also prolongs hexobarbital sleeping time, produces ataxia and has a disruptive effect on EEG activity and conditioned behaviour. Amitriptyline antagonizes or reverses the depressant effects of reserpine and tetrabenazine and potentiates the pressor effects of norepinephrine and various behavioural effects of amphetamine. It possesses anticholinergic, antihistaminic and weak antiserotonin action. Amitriptyline also decreases body temperature, lowers blood pressure in the anesthetized dog and has a quinidine-like effect on the heart.
Amitriptyline is absorbed slowly from the gastrointestinal tract in experimental animals. The drug is distributed in liver, lung, and brain tissue. Amitriptyline is detoxified in the liver where it undergoes N-demethylation to nortriptyline, which is further demethylated. Amitriptyline is excreted in the urine and bile as conjugates of the cis and trans isomers of 10-hydroxynortriptyline.
TOXICOLOGY
Acute:
Species Route Sex LD50
(mg of base/kg)
95% Fiducial Limits
Mice PO F 289 (249-335)
IP F 76 (71-81) SC F 328 (279-386)
Rats PO F 464 (370-583)
PO M 600 (403-872) IP F 67 (59-76) IP M 77 (67-88) SC F 1350 (1130-1162) SC M 1235 (1010-1510)
Signs of toxicity included sedation, ataxia, ptosis, lacrimation, decreased respiratory rate, partial loss of righting reflex and convulsions.
Subacute and Chronic:
Dogs: Oral doses of 20 and 40 mg/kg/day were tolerated for 6 months without hematologic, biochemical or anatomical evidence of drug toxicity. Signs of drug effect included slight to marked sedation, a slight tachycardia, slight ataxia, and occasionally, excessive salivation and emesis. Oral doses of 80 mg/kg/day in a 6-month study were not well tolerated: 2 of 4 dogs died within 3 weeks after exhibiting severe ataxia and sedation. No other drug-related effects were observed. Doses of 100 mg/kg/day or greater were not tolerated for more than a few days. The only effect observed was a small amount of fat in the periportal region of the liver without evidence of necrosis.
Rats: 0, 15, 30 or 60 mg/kg/day were given orally by gavage, 5 days a week, for periods up to 48 weeks. Doses of 60 mg/kg/day produced a moderate depression of body weight and a slight increase in liver weight.
REFERENCES:
- 1.
Product Monograph, Apo-Amitriptyline (amitriptyline hydrochloride) Tablets, Apotex Inc.,
February 11, 2019.
- 2.
A Two-Way Crossover, Blinded, Single-Dose, Fasting, Bioequivalence Study of Amitriptyline
50mg Tablets Versus Apo®-Amitriptyline 50mg Tablets in Normal Healthy Non-Smoking Male Subjects (Study# 3300). Data on File at Teva Canada Limited.