


Product Monograph - Tigecycline
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 11/2023 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ..................................................................................................................... 5
1.2 Geriatrics ..................................................................................................................... 5
2 CONTRAINDICATIONS ...................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................................. 5
4 DOSAGE AND ADMINISTRATION ...................................................................................... 6
4.1 Dosing Considerations ................................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ............................................................. 6
4.3 Reconstitution ............................................................................................................. 7
4.4 Administration ............................................................................................................. 8
4.5 Missed Dose ................................................................................................................. 9
5 OVERDOSAGE ................................................................................................................ 10
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.................................... 10
7 WARNINGS AND PRECAUTIONS ..................................................................................... 10
7.1 Special Populations .................................................................................................... 14
7.1.1 Pregnant Women ....................................................................................................... 14
7.1.2 Breast-feeding ........................................................................................................... 15
7.1.3 Pediatrics ................................................................................................................... 15
7.1.4 Geriatrics ................................................................................................................... 15
8 ADVERSE REACTIONS ..................................................................................................... 15
8.1 Adverse Reaction Overview ....................................................................................... 15
8.2 Clinical Trial Adverse Reactions ................................................................................. 16
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .............................................................. 19
8.3 Less Common Clinical Trial Adverse Reactions .......................................................... 19
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ....................................... 20
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................... 20
8.5 Post-Market Adverse Reactions ................................................................................. 20
9 DRUG INTERACTIONS ..................................................................................................... 21
9.2 Drug Interactions Overview ....................................................................................... 21
9.3 Drug-Behavioural Interactions ................................................................................... 21
9.4 Drug-Drug Interactions .............................................................................................. 21
9.5 Drug-Food Interactions .............................................................................................. 23
9.6 Drug-Herb Interactions .............................................................................................. 23
9.7 Drug-Laboratory Test Interactions ............................................................................. 23
10 CLINICAL PHARMACOLOGY ............................................................................................ 23
10.1 Mechanism of Action ................................................................................................. 23
10.2 Pharmacodynamics .................................................................................................... 23
10.3 Pharmacokinetics ....................................................................................................... 23
11 STORAGE, STABILITY AND DISPOSAL .............................................................................. 27
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................... 27
PART II: SCIENTIFIC INFORMATION ....................................................................................... 28
13 PHARMACEUTICAL INFORMATION ................................................................................ 28
14 CLINICAL TRIALS ............................................................................................................. 28
14.1 Clinical Trials by Indication ......................................................................................... 28
15 MICROBIOLOGY ............................................................................................................. 35
16 NON-CLINICAL TOXICOLOGY .......................................................................................... 41
17 SUPPORTING PRODUCT MONOGRAPHS......................................................................... 68
PATIENT MEDICATION INFORMATION .................................................................................. 69
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TIGECYCLINE (tigecycline) is indicated for the treatment of the following infections when caused by susceptible strains of the designated microorganisms in patients 18 years of age and older:
Complicated skin and skin structure infections (cSSSI) caused by Escherichia coli, Enterococcus faecalis (vancomycin-susceptible strains only), Staphylococcus aureus (methicillin-susceptible and-resistant strains), Streptococcus agalactiae, Streptococcus anginosus, Streptococcus pyogenes, Enterobacter cloacae, Klebsiella pneumoniae, and Bacteroides fragilis.
Patients with severe underlying disease, such as those who were immunocompromised, patients with decubitus ulcer infections, or patients who had infections requiring longer than 14 days of treatment (for example, necrotizing fasciitis), were not enrolled in clinical trials.
- Complicated intra-abdominal infections (cIAI) caused by Citrobacter freundii, Enterobacter cloacae, Escherichia coli, Klebsiella oxytoca, Klebsiella pneumoniae, Enterococcus faecalis (vancomycin-susceptible strains only), Staphylococcus aureus (methicillin-susceptible only), Streptococcus anginosus grp. (includes S. anginosus, S. intermedius, and S. constellatus), Bacteroides fragilis, Bacteroides thetaiotaomicron, Bacteroides uniformis, Bacteroides vulgatus, Clostridium perfringens, and Peptostreptococcus micros.
- Community acquired pneumonia (CAP) (mild to moderate infections only) caused by Haemophilus influenzae, Streptococcus pneumoniae (penicillin-susceptible isolates only), Mycoplasma pneumoniae, and Chlamydia pneumoniae.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of TIGECYCLINE and other antibacterial drugs, TIGECYCLINE should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Appropriate specimens for bacteriological examination should be obtained in order to isolate and identify the causative organisms and to determine their susceptibility to tigecycline. Once these results are available, antimicrobial therapy should be adjusted if necessary. TIGECYCLINE may be initiated as empiric therapy before results of these tests are known. Tigecycline has decreased in vitro activity against Proteus spp., Providencia spp., and Morganella spp. Pseudomonas aeruginosa is inherently resistant to TIGECYCLINE.
Limitations of Use: TIGECYCLINE is not indicated for the treatment of:
- diabetic foot infections
- hospital-acquired (HAP) or ventilator-associated pneumonia (VAP)
- severe community acquired pneumonia
See 7 WARNINGS AND PRECAUTIONS, General.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is not associated with differences in safety or effectiveness. A brief discussion can be found in 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
TIGECYCLINE (tigecycline) is contraindicated in patients who are hypersensitive to tigecycline or tetracycline class of antibiotics or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Based on pharmacokinetic data in patients with severe hepatic impairment (Child Pugh C), the dose of TIGECYCLINE (tigecycline) should be altered. See 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
4.2 Recommended Dose and Dosage Adjustment
Health Canada has not authorized an indication for pediatric use.
The recommended dosage regimen of TIGECYCLINE is an initial dose of 100 mg, followed by 50 mg every 12 hours. Intravenous (IV) infusions of TIGECYCLINE should be administered over approximately 30 to 60 minutes every 12 hours.
The recommended duration of treatment with TIGECYCLINE for cSSSI or for cIAI is 5 to 14 days.
The recommended duration of treatment with TIGECYCLINE for CAP (mild to moderate infections only) is 7 to 14 days.
The duration of therapy should be guided by the severity and site of the infection and the patient’s clinical and bacteriological progress.
Patients with Hepatic Insufficiency
No dosage adjustment of TIGECYCLINE is warranted in patients with mild to moderate hepatic impairment (Child Pugh A and Child Pugh B). See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency.
Patients with Severe Hepatic Impairment
Based on the pharmacokinetic profile of tigecycline in patients with severe hepatic impairment (Child Pugh C), the dose of TIGECYCLINE should be altered to 100 mg followed by 25 mg every 12 hours. Patients with severe hepatic impairment (Child Pugh C) should be treated with caution and monitored for treatment response. See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency.
Patients with Renal Insufficiency
Based on the pharmacokinetic data, no dosage adjustment of TIGECYCLINE is necessary in patients with renal impairment or in patients undergoing hemodialysis. See 10 CLINICAL
PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency.
Other
No dosage adjustment of TIGECYCLINE is necessary based on age (adults 18 years of age or more), gender or race. See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions.
4.3 Reconstitution
Parenteral Products:
Table 1 – Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Concentration per mL |
|---|---|---|---|
| 5 mL | 5.3 mL | 5 mL | 10 mg/mL* |
*The pH of the reconstituted solution is 4.5 to 5.5.
Each Vial of TIGECYCLINE should be reconstituted with 5.3 mL of 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP, or, Lactated Ringer’s Injection, USP to achieve a concentration of 10 mg/mL of tigecycline. (Note: Each vial contains a 6% overage. Thus, 5 mL of reconstituted solution is equivalent to 50 mg of the drug.) The vial should be gently swirled until the drug dissolves.
Dilution:
Withdraw 5 mL of the reconstituted solution from the vial and add to a 100 mL IV bag for infusion (for a 100 mg dose, reconstitute two vials; for a 50 mg dose, reconstitute one vial). The maximum concentration in the IV bag should be 1 mg/mL. The reconstituted solution should be yellow to orange in color; if not, the solution should be discarded. Parenteral drug products should be inspected visually for particulate matter and discoloration (e.g., green or black) prior to administration, whenever solution and container permit.
Compatible intravenous solutions include 0.9% Sodium Chloride Injection, USP, 5% Dextrose Injection USP, and Lactated Ringer’s Injection, USP.
Once reconstituted, TIGECYCLINE may be stored at room temperature (not to exceed 25°C/77°F) for up to 24 hours (up to 6 hours in the vial and the remaining time in the IV bag). Alternatively, TIGECYCLINE mixed with 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection USP may be stored refrigerated at 2°C to 8°C (36°F to 46°F) for up to 48 hours following immediate transfer of the reconstituted solution into the IV bag. See 11 STORAGE, STABILITY AND DISPOSAL.
If the storage conditions exceed 25°C/77°F after reconstitution, tigecycline should be used immediately.
The concentration of the admixture solution is 1 mg/mL (100 mg loading dose/100 mL) or 0.5 mg/mL (50 mg dose in 100 mL).
4.4 Administration
Intravenous (IV) infusions of TIGECYCLINE should be administered over approximately 30 to 60 minutes every 12 hours.
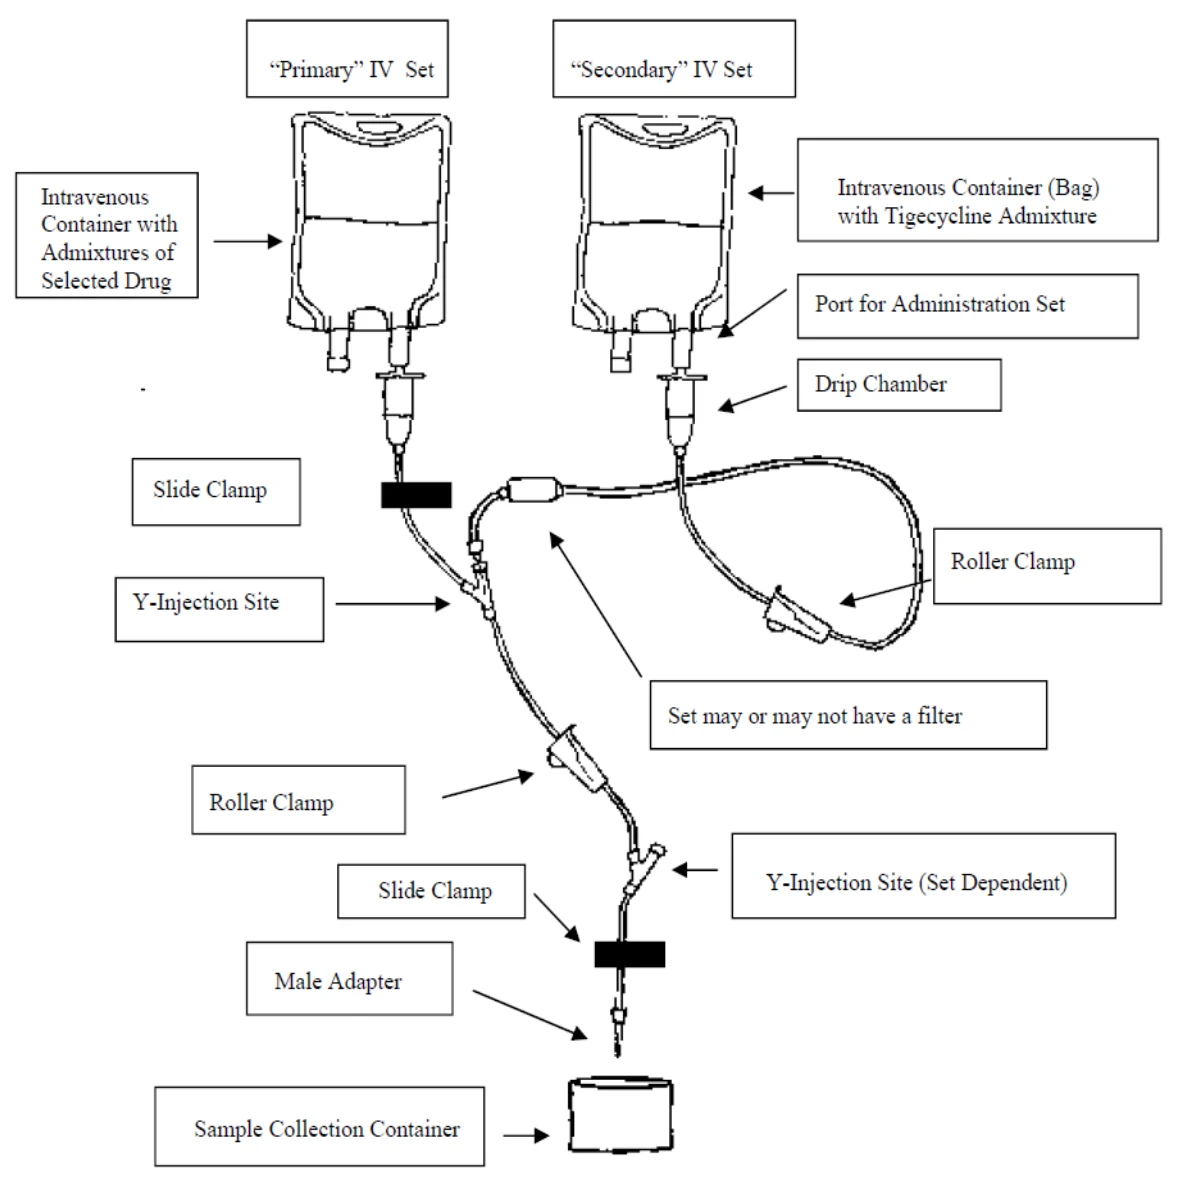
TIGECYCLINE may be administered intravenously through a dedicated line or through a Y-site. If the same intravenous line is used for sequential infusion of several drugs, the line should be flushed before and after infusion of TIGECYCLINE with either 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP. Injection should be made with an infusion solution compatible with TIGECYCLINE and with any other drug(s) administered via this common line.
When administered through a Y-site, TIGECYCLINE, is compatible with the following drugs or diluents when used with either 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection USP:
- Dopamine HCl Injection, USP (1.6 mg/mL in 0.9% Sodium Chloride Injection)
- Lidocaine HCl Injection, USP (2.0 mg/mL in 0.9% Sodium Chloride Injection)
- Lactated Ringer’s Injection, USP (250 mL bag)
- Potassium Chloride Injection concentrate, USP (0.04 mEq/mL in 0.9% Sodium Chloride Injection)
- Ranitidine Injection, USP (0.6 mg/mL in 0.9% Sodium Chloride Injection)
- Theophylline (1.6 mg/mL in 5% Dextrose Injection)
- Dobutamine Injection, USP (1.0 mg/mL in 0.9% Sodium Chloride Injection)
Amikacin sulphate Injection, USP (2.5 mg/mL and 5.0 mg/mL in 0.9% Sodium Chloride
Injection)
- Gentamicin Injection, USP (1.4 mg/mL in 0.9% Sodium Chloride Injection)
- Tobramycin Injection, USP (1.4 mg/mL in 0.9% Sodium Chloride Injection)
- Haloperidol Injection, USP (0.2 mg/mL in 0.9% Sodium Chloride Injection)
- Metoclopramide Injection, USP (3 mg/mL in 0.9% Sodium Chloride Injection)
- Morphine sulphate Injection, USP (0.5 mg/mL in 0.9% Sodium Chloride Injection)
- Norepinephrine bitartrate Injection, USP (4 mcg/mL in 5% Dextrose Injection)
- Propofol Injectable Emulsion 1% (10 mg/mL in 0.9% Sodium Chloride Injection)
- Piperacillin sodium /tazobactam sodium (EDTA formulation) powder for injection (Piperacillin 40 mg/tazobactam 5 mg/mL in 0.9% Sodium Chloride Injection)
The following drugs should not be administered simultaneously through the same Y-site as TIGECYCLINE: amphotericin B, amphotericin B lipid complex, diazepam, esomeprazole and omeprazole.
A generic schematic diagram for the Y-site co-administration is provided below:
Figure 1: A generic schematic diagram for the Y-site co-administration
4.5 Missed Dose
This information is not available for this drug product.
5 OVERDOSAGE
No specific information is available on the treatment of overdose with TIGECYCLINE (tigecycline). Intravenous administration of tigecycline at a single dose of 300 mg over 60 minutes in healthy volunteers resulted in an increased incidence of nausea and vomiting. In single-dose IV toxicity studies conducted with tigecycline in mice, the estimated median lethal dose (LD50) was 124 mg/kg in males and 98 mg/kg in females. In rats, the estimated LD50 was 106 mg/kg for both sexes. Tigecycline is not removed in significant quantities by hemodialysis.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Intravenous infusion | Sterile, lyophilized powder 50 mg tigecycline per vial | Hydrochloric acid, lactose monohydrate, sodium hydroxide |
TIGECYCLINE (tigecycline) for injection is supplied in a single-dose 5 mL Type I glass vial.
TIGECYCLINE is an orange lyophilized powder or cake. Each TIGECYCLINE vial contains 50 mg tigecycline lyophilized powder for intravenous infusion and 100 mg of lactose monohydrate. The pH is adjusted with hydrochloric acid, and if necessary, sodium hydroxide. The product does not contain preservatives.
Supplied 10 vials per box.
7 WARNINGS AND PRECAUTIONS
General
All-Cause Mortality
An increase in all-cause mortality has been observed in a meta-analysis of Phase 3 and 4 clinical trials in tigecycline-treated patients versus comparator-treated patients. In all 13 Phase 3 and 4 trials that included a comparator, death occurred in 4.0% (150/3788) of patients receiving tigecycline and 3.0% (110/3646) of patients receiving comparator drugs. In a pooled analysis of these trials, based on a random effects model by trial weight, an adjusted risk difference of all-cause mortality was 0.6% (95% CI 0.1, 1.2) between tigecycline and comparator-treated patients. An analysis of mortality in all trials conducted for approved indications (cSSSI, cIAI, and CAP), including post-market trials showed an adjusted mortality rate of 2.5% (66/2640) for tigecycline and 1.8% (48/2628) for comparator, respectively. The adjusted risk difference for mortality stratified by trial weight was 0.6% (95% CI 0.0, 1.2).
The cause of this mortality difference has not been established. Generally, deaths were the result of worsening infection, complications of infection or underlying co-morbidities.
Tigecycline should be reserved for use in situations when alternative treatments are not suitable. See 8 ADVERSE REACTIONS, 8.2 Clinical Trial Adverse Reactions, Adverse events with outcome of Death.
Glycylcycline antibiotic class effects
Glycylcycline class antibiotics are structurally similar to tetracycline class antibiotics and may have similar adverse events. Such effects may include photosensitivity, pseudotumor cerebri, pancreatitis, and anti-anabolic action (which has led to increased BUN, azotemia, acidosis, and hyperphosphatemia).
Superinfection
During antibiotic therapy, colonization or superinfection with Candida, Proteus or Pseudomonas spp may occur in the GI, genitourinary, and respiratory tracts. Patients should be carefully monitored during therapy. If superinfection occurs, appropriate measures should be taken.
Cardiovascular
An effect on cardiac repolarization following tigecycline administration cannot be definitively excluded from the clinical data. See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Cardiovascular.
There is limited clinical experience using tigecycline in patients with known prolongation of the QTc interval, patients with hypokalemia, patients receiving Class IA (e.g. quinidine, procainamide) or Class III (e.g., amiodarone, sotalol) antiarrhythmic agents, or in other pro-arrhythmic conditions.
Pharmacokinetic studies between tigecycline and drugs that prolong the QTc interval such as cisapride, erythromycin, antipsychotics, and tricyclic antidepressants have not been performed. The effect of tigecycline has also not been studied in patients with congenital prolongation of the QT interval. It is expected that these individuals may be more susceptible to drug-induced QT prolongation.
The magnitude of QTc prolongation may increase with increasing concentrations of drugs; therefore, the recommended dose and the recommended infusion rate for TIGECYCLINE should not be exceeded. See 4 DOSAGE AND ADMINISTRATION.
Patients should be instructed to contact their physician if they experience palpitations or fainting spells while taking TIGECYCLINE.
Driving and Operating Machinery
Tigecycline can cause dizziness. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Gastrointestinal
Clostridium difficile-associated disease
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including tigecycline. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases. See 8 ADVERSE REACTIONS.
Intra-abdominal infections
Caution should be exercised when considering tigecycline monotherapy in patients with complicated intra-abdominal infections (cIAI) secondary to clinically apparent intestinal perforation. See 8 ADVERSE REACTIONS. In Phase 3 cIAI studies (n=1642), 6 patients treated with tigecycline and 2 patients treated with imipenem/cilastatin presented with intestinal perforations and developed sepsis/septic shock. The 6 patients treated with tigecycline had higher APACHE II scores (median = 13) vs the 2 patients treated with imipenem/cilastatin (APACHE II scores = 4 and 6). Due to differences in baseline APACHE II scores between treatment groups and small overall numbers, the relationship of this outcome to treatment cannot be established.
Hepatic/Biliary/Pancreatic
Increases in total bilirubin concentration, prothrombin time and transaminases have been seen in patients treated with tigecycline. Isolated cases of significant hepatic dysfunction and hepatic failure have been reported in patients treated with tigecycline. Patients who develop abnormal liver function tests during tigecycline therapy should be monitored for evidence of worsening hepatic function and evaluated for risk/benefit of continuing tigecycline therapy. Adverse events may occur after the drug has been discontinued.
Acute pancreatitis, including fatal cases, have occurred in association with tigecycline treatment. See 8 ADVERSE REACTIONS, 8.5 Post Market Adverse Reactions. The diagnosis of acute pancreatitis should be considered in patients taking tigecycline who develop clinical symptoms, signs, or laboratory abnormalities suggestive of acute pancreatitis. Cases have been reported in patients without known risk factors for pancreatitis. Patients usually improve after tigecycline discontinuation. Consideration should be given to the cessation of the treatment with tigecycline in cases suspected of having developed pancreatitis.
Immune
Hypersensitivity
Anaphylaxis/anaphylactoid reactions have been reported with tigecycline and may be life-threatening.
Monitoring and Laboratory Tests
The use of tigecycline with other drugs may lead to drug-drug interactions and require dose adjustment and monitoring. See 9 DRUG INTERACTIONS.
Monitoring of blood coagulation parameters, including blood fibrinogen, is recommended prior to treatment initiation with tigecycline and regularly while on treatment.
Prothrombin time or other suitable anticoagulation test should be monitored if tigecycline is administered with warfarin.
Monitoring of calcineurin inhibitor (tacrolimus, cyclosporine) blood levels before, during and following treatment with tigecycline, together with appropriate dose adjustment, is recommended. See 9 DRUG INTERACTIONS, 9.2 Drug Interactions Overview.
Reproductive Health: Female and Male Potential
- Fertility
The effects of tigecycline on fertility in humans have not been studied.
Respiratory
Mortality imbalance and lower cure rates in hospital-acquired pneumonia
TIGECYCLINE is not indicated for treatment of hospital acquired pneumonia (HAP). The safety and efficacy of tigecycline in patients with HAP have not been established. In a study of hospital acquired pneumonia patients, the sub-group of patients with ventilator-associated pneumonia (VAP) who received tigecycline had lower cure rates (47.9% versus 70.1% for the clinically evaluable population) and greater mortality (25/131 [19.1%] versus 15/122 [12.3%]) than the comparator. Of those patients with VAP and bacteremia at baseline, those who received tigecycline had greater mortality (9/18 [50.0%] versus 1/13 [7.7%]) than the comparator.
TIGECYCLINE is not indicated for the treatment of severe community acquired pneumonia. Safety and efficacy of tigecycline in severe community acquired pneumonia have not been studied. See 14 CLINICAL TRIALS. Tigecycline has not been evaluated in clinical trials for use against suspected or documented multiple drug resistant pathogens in pneumonia.
Sensitivity/Resistance
Development of Drug Resistant Bacteria
Prescribing TIGECYCLINE in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Skin
TIGECYCLINE is not indicated for the treatment of diabetic foot infections. The safety and efficacy of tigecycline in patients with diabetic foot infections have not been established.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies of tigecycline in pregnant women. TIGECYCLINE should not be used unless the potential benefit to the mother outweighs any possible risk to the fetus.
Tigecycline may cause fetal harm when administered to a pregnant woman. Results of animal studies indicate that tigecycline crosses the placenta and is found in fetal tissues. Tigecycline was not teratogenic in the rat or rabbit. Decreased fetal weights and increased incidence of minor skeletal anomalies in rats and rabbits (with associated delays in ossification) have been observed with tigecycline. Tigecycline may be associated with permanent tooth discoloration in humans during tooth development (last half of pregnancy, infancy, and childhood to the age of 8 years). Results of studies in rats with tigecycline have shown bone discoloration.
See 16 NON-CLINICAL TOXICOLOGY.
Tigecycline has not been studied for use during labor and delivery.
7.1.2 Breast-feeding
It is not known whether this drug is excreted in human milk. Available data in animals have shown excretion of tigecycline/metabolites in milk. See 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology. Because many drugs are excreted in human milk, and there is the potential risk of permanent discoloration of the teeth/bones (yellow gray- brown) of the child, TIGECYCLINE should not be administered to a nursing woman unless the potential benefit to the mother outweighs any possible risk to the child.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. Pediatric clinical trials to evaluate the safety and efficacy of tigecycline were not conducted because of the higher risk of mortality seen in adult trials. Tigecycline can cause teeth discoloration in children less than 8 years of age. See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Pediatrics.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Of the total number of subjects who received tigecycline in Phase 3 clinical studies (n=2514), 664 were 65 years of age and over, while 288 were 75 years of age and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, but greater sensitivity to adverse events in some older individuals cannot be ruled out.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The overall incidence of drug-related adverse reactions with tigecycline was 41.0%. The most common adverse drug reactions, as judged by investigators, in patients treated with tigecycline were nausea at 18.9% (11.6% mild; 6.4% moderate; 0.9% severe) and vomiting 12.4% (7.4% mild; 4.3% moderate; 0.6% severe). In general, nausea and vomiting occurred early in treatment (Days 1 to 2) and on average over 2 to 4 days.
Tigecycline was discontinued due to an adverse event in 6.7% of subjects. Discontinuation from tigecycline was most frequently associated with nausea (1.1%) and vomiting (1.1%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In Phase 3 clinical studies, 2514 patients were treated with tigecycline. These patients received at least 1 dose of tigecycline. In the active controlled studies that employed a 1:1 randomization, 2274 patients with complicated intra-abdominal infections, complicated skin and skin structure infections, community acquired pneumonia, and hospital acquired pneumonia were treated with tigecycline for up to 14 days (see 14 CLINICAL TRIALS). In resistant pathogen clinical studies which were uncontrolled or employed a randomization of 3:1, 184 patients were treated for up to 14 days and 56 patients up to 28 days.
Table 3 shows the incidence (%) of treatment-emergent adverse drug reactions (as judged by the investigators) reported in ≥1% of patients treated with tigecycline in Phase 3 clinical studies.
Table 3 - Incidence (%) of Adverse Drug Reactions Reported in ≥1% of Patients Treated with Tigecycline in Phase 3 Clinical Studies
| Adverse Events | Tigecyclinea (N=2514) | Comparator (N=2307) |
|---|---|---|
| Any adverse event | 41.0 | 32.4 |
| Body as a whole | 6.2 | 6.1 |
| Abdominal pain | 1.2 | 0.6 |
| Headache | 1.2 | 1.7 |
| Cardiovascular system | 3.7 | 5.0 |
| Phlebitis | 1.5 | 2.3 |
| Digestive system | 27.2 | 14.9 |
| Nausea | 18.9 | 7.8 |
| Vomiting | 12.4 | 4.2 |
| Diarrhea | 6.2 | 4.9 |
| Anorexia | 1.1 | 0.2 |
| Liver function tests abnormal | 1.0 | 0.8 |
Adverse Events
Tigecyclinea (N=2514) | Comparator (N=2307) | |
|---|---|---|
| Hemic and lymphatic system | 6.0 | 5.0 |
| Thrombocythemia | 2.1 | 1.8 |
| Activated partial thromboplastin time prolonged | 1.0 | 0.4 |
| Metabolic and nutritional | 8.7 | 7.5 |
| Lactic dehydrogenase increased | 1.4 | 1.0 |
| Alkaline phosphatase increased | 1.9 | 1.5 |
| SGPT increasedb | 2.5 | 3.4 |
| SGOT increasedb | 2.2 | 3.3 |
| Amylase increased | 1.4 | 1.0 |
| Bilirubinemia | 1.3 | 0.2 |
| Skin and appendages | 2.7 | 3.8 |
| Rash | 1.2 | 1.7 |
| Urogenital system | 1.4 | 0.8 |
| Vaginal moniliasis | 1.0 | 0.6 |
a. 100 mg initially, followed by 50 mg every 12 hours.
b. Liver function test abnormalities in tigecycline-treated patients were reported more frequently in the posttherapy period than those in comparator-treated patients, which occurred more often on therapy.
Abbreviations: SGPT=serum glutamic pyruvic transaminase; SGOT=serum glutamic oxaloacetic transaminase.
Adverse events with outcome of Death
In a pooled analysis of all 13 Phase 3 and 4 trials that included a comparator, death occurred in 4.0% (150/3788) of patients receiving tigecycline and 3.0% (110/3646) of patients receiving comparator drugs. In a pooled analysis of these trials, based on a random effects model by trial weight, an adjusted risk difference of all-cause mortality was 0.6% (95% CI 0.1, 1.2) between tigecycline-treated and comparator-treated patients. Risk differences in the treatments by infection type are provided in Table 4. The cause of the imbalance has not been established. Generally, deaths were the result of worsening infections or complications of infection or underlying co-morbidities.
Table 4 - Patients with Adverse Events with Outcome of Death by Infection Type
| Tigecycline | Comparator | Risk Differencea | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Infection Type | n/N | % | n/N | % | % (95% CI) | |||||||||||
| cSSSI | 12/834 | 1.4 | 6/813 | 0.7 | 0.7 (-0.5, 1.9) | |||||||||||
| cIAI | 42/1382 | 3.0 | 31/1393 | 2.2 | 0.8 (-0.4, 2.1) | |||||||||||
| CAP | 12/424 | 2.8 | 11/422 | 2.6 | 0.2 (-2.3, 2.7) | |||||||||||
| HAP | 66/467 | 14.1 | 57/467 | 12.2 | 1.9 (-2.6, 6.4) | |||||||||||
| Non-VAPb | 41/336 | 12.2 | 42/345 | 12.2 | 0.0 (-5.1, 5.2) | |||||||||||
| VAPb | 25/131 | 19.1 | 15/122 | 12.3 | 6.8 (-2.9, 16.2) | |||||||||||
| MRSA/VRE (RP)* | 11/128 | 8.6 | 2/43 | 4.7 | 3.9 (-9.1, 11.6) | |||||||||||
| DFI | 7/553 | 1.3 | 3/508 | 0.6 | 0.7 (-0.8, 2.2) | |||||||||||
| Overall Adjusted | 150/3788 | 4.0 | 110/3646 | 3.0 | 0.6 (0.1, 1.2) c | |||||||||||
CAP = Community-acquired pneumonia; cIAI = Complicated intra-abdominal infections; cSSSI = Complicated skin and skin structure infections; HAP = Hospital-acquired pneumonia; VAP = Ventilator-associated pneumonia; MRSA/VRE= Resistant gram-positive pathogen study in patients with MRSA or Vancomycin Resistant Enterococcus (VRE); DFI=diabetic foot infections.
a The difference between the percentage of patients who died in tigecycline and comparator treatment groups. The 95% CIs were calculated using the Wilson Score Method with continuity correction.
b These are subgroups of the HAP population
c Overall adjusted (random effects model by trial weight) risk difference estimate and 95% CI
Note: The studies include 300, 305, 900 (cSSSI), 301,306, 315, 316, 400 (cIAI), 308 and 313 (CAP), 311 (HAP), *307 [Resistant gram-positive pathogen study in patients with MRSA or Vancomycin Resistant Enterococcus (VRE)], and 319 (DFI with or without osteomyelitis).
An analysis of mortality in all trials conducted for approved indications (cSSSI, cIAI, and CAP), including post-market trials (315, 400, 900) showed an adjusted mortality rate of 2.5% (66/2640) for tigecycline and 1.8% (48/2628) for comparator, respectively. The adjusted risk difference for mortality stratified by trial weight was 0.6% (95% CI 0.0, 1.2).
Infection-related serious adverse events
In Phase 3 clinical studies, infection-related serious adverse events were more frequently reported for subjects treated with tigecycline (6.7%) vs comparators (5.5%). Serious adverse events of sepsis/septic shock were more frequently reported for subjects treated with tigecycline (1.8%) vs comparators (1.2%). Due to baseline differences between treatment groups in this subset of patients, the relationship of this outcome to treatment cannot be established. See 7 WARNINGS AND PRECAUTIONS, General. Other events included abscess
(1.4% vs 1.2%), infections, including wound infections (1.2% vs 0.9%) and pneumonia (1.1% vs 1.2%) for tigecycline vs comparators, respectively.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
This information is not available for this drug product.
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse drug reactions as judged by the investigators were reported infrequently (<1% and ≥0.1%) in patients receiving tigecycline in Phase 3 clinical studies:
Body as a whole: infection, fever, asthenia, septic shock, injection site inflammation, injection site pain, injection site reaction, chills, injection site edema, injection site phlebitis, pain, moniliasis, chest pain, chills and fever, malaise, peritonitis, allergic reaction
Cardiovascular system: thrombophlebitis, hypertension, hypotension, bradycardia, vasodilatation, tachycardia, atrial fibrillation, AV block first degree, congestive heart failure, electrocardiogram abnormal, palpitation, QT interval prolonged, sinus bradycardia, syncope, tachycardia sinus, ventricular extrasystoles
Digestive system: dyspepsia, oral moniliasis, constipation, dry mouth, jaundice, stools abnormal, abdominal distension, fecal incontinence, flatulence, gastroesophageal reflux disease, glossitis, hepatic failure, liver damage, mucositis, pancreatitis, pseudomembranous colitis
Hemic and lymphatic system: eosinophilia, prothrombin time prolonged, anemia, leukocytosis, leukopenia, international normalized ratio increased, thrombocytopenia, coagulation disorder, ecchymosis, hemolysis, neutropenia, prothrombin decreased, prothrombin time shortened
Metabolic and nutritional: BUN increased, hypoproteinemia, creatinine increased, hypocalcemia, hyperkalemia, hyponatremia, peripheral edema, hypoglycemia, hypokalemia, creatine phosphokinase increased, healing abnormal, hyperglycemia, hyperphosphatemia, hypophosphatemia
Musculoskeletal system: myalgia
Nervous system: dizziness, somnolence, insomnia, nervousness, tremor, twitching, vertigo
Respiratory system: cough increased, dyspnea, hiccup, pleural effusion, pneumonia, pulmonary physical finding, pharyngitis, sputum increased
Skin and appendages: pruritus, sweating, urticaria, fungal dermatitis, herpes simplex, maculopapular rash, pruritic rash, skin discoloration
Special senses: taste perversion, abnormal vision
Urogenital system: vaginitis, kidney function abnormal, urinary tract infection, creatinine clearance decreased, leukorrhea, polyuria, scrotal edema, vulvovaginal disorder, vulvovaginitis
Adverse events associated with miscellaneous factors: local reaction to procedure, device malfunction
In addition to those noted above, the following adverse reactions judged as related as determined by the investigator were noted in Phase 2 studies in complicated skin and skin structure infections and complicated intra-abdominal infections: hypomagnesemia, confusion.
Adverse reactions for the Phase 1 clinical pharmacology studies are similar to those reported in Phase 3 and Phase 2 clinical trials. The most common adverse reactions in these trials were nausea, vomiting, headache, dizziness, and diarrhea.
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
This information is not available for this drug product.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
See Table 3.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post approval use of tigecycline:
Acute pancreatitis including fatal cases, anaphylaxis/anaphylactoid reactions, severe skin reactions including Stevens-Johnson Syndrome, thrombocytopenia, hepatic cholestasis and hypofibrinogenemia (including bleeding events, some serious).
There has been one case of ventricular arrhythmia (with positive dechallenge and rechallenge) associated with tigecycline administration.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Tacrolimus, cyclosporine (calcineurin inhibitors): Clinically significant increases in blood trough concentrations of tacrolimus and cyclosporine requiring dose adjustment, have been reported with concomitant use of tigecycline. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions.
In vitro studies in human liver microsomes indicate that tigecycline does not inhibit metabolism mediated by any of the following 6 cytochrome (CYP) P450 isoforms: 1A2, 2C8, 2C9, 2C19, 2D6, and 3A4. There has been no specific study conducted to examine the effects of tigecycline on microsomal enzyme induction. The exposure and safety data did not show any evidence of increased liver weight during multiple dosing which typically is associated with enzyme induction. Therefore, tigecycline is not expected to alter the metabolism of drugs metabolized by these enzymes. In addition, because tigecycline is not extensively metabolized, clearance of tigecycline is not expected to be affected by drugs that inhibit or induce the activity of these CYP450 isoforms.
In vitro studies using Caco-2 cells indicate that tigecycline does not inhibit digoxin flux, suggesting that tigecycline is not a P-glycoprotein (P-gp) inhibitor. This in vitro information is consistent with the lack of effect of tigecycline on digoxin clearance noted in the in vivo drug interaction study described below.
Tigecycline is a substrate of P-gp based on an in vitro study using a cell line overexpressing P-gp. The potential contribution of P-gp-mediated transport to the in vivo disposition of tigecycline is not known. Coadministration of P-gp inhibitors (e.g., ketoconazole or cyclosporine) or P-gp inducers (e.g., rifampicin) could affect the pharmacokinetics of tigecycline.
9.3 Drug-Behavioural Interactions
This information is not available for this drug product.
9.4 Drug-Drug Interactions
Table 5 - Established or Potential Drug-Drug Interactions
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| tacrolimus | C | Increased tacrolimus trough blood levels 3.2 to 3.8-fold within 1 to 10 days of tigecycline initiation. | Tacrolimus dose adjustment during and following tigecycline therapy, based on therapeutic concentration monitoring, is recommended. Two case reports described |
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| implementing a reduction in the tacrolimus daily dose from 7 mg to 2 mg during tigecycline therapy, and a dose increase upon cessation of tigecycline therapy. In one of the two cases, the tacrolimus dose reduction followed withholding tacrolimus for 2 days. | |||
| cyclosporine | C | Increased cyclosporine trough blood levels 1.4-fold within 4 days of tigecycline initiation. | Cyclosporine dose adjustment, during and following tigecycline therapy, based on therapeutic concentration monitoring, is recommended. One case report described withholding cyclosporine for one day, followed by a reduction in the cyclosporine daily dose from 120 mg to 60 mg, during tigecycline therapy, and a dose increase upon cessation of tigecycline therapy. |
| Legend: C = Case Study; CT = Clinical Trial; T = Theoretical | |||
Concurrent use of antibiotics with oral contraceptives may render oral contraceptives less effective.
Tigecycline (100 mg followed by 50 mg every 12 hours) and digoxin (0.5 mg followed by 0.25 mg every 24 hours) were coadministered to healthy subjects in a drug interaction study. Tigecycline slightly decreased the Cmax of digoxin by 13%, but did not affect the AUC or clearance of digoxin. This small change in Cmax did not affect the steady state pharmacodynamic effects of digoxin as measured by changes in ECG intervals. In addition, digoxin did not affect the pharmacokinetic profile of tigecycline. Therefore, no dosage adjustment is necessary when tigecycline is administered with digoxin.
Concomitant administration of tigecycline (100 mg followed by 50 mg every 12 hours) and warfarin (25 mg single-dose) to healthy subjects resulted in a decrease in clearance of R-warfarin and S-warfarin by 40% and 23%, and an increase in AUC by 68% and 29%, respectively. Tigecycline did not significantly alter the effects of warfarin on INR. In addition, warfarin did not affect the pharmacokinetic profile of tigecycline. However, prothrombin time or other suitable anticoagulation test should be monitored if tigecycline is administered with warfarin.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Tigecycline, a glycylcycline, acts by inhibiting protein synthesis at the level of the bacterial ribosome by blocking the binding of amino-acyl tRNA to the A site of the ribosome. Tigecycline has in vivo and in vitro antibacterial activity against a broad-spectrum of pathogens. See 15 MICROBIOLOGY. Tigecycline is active against bacterial strains that carry classical tetracycline resistant genes encoding either ribosomal protection or a tetracycline efflux pump. Several efflux-related resistance mechanisms have been identified that provide decreased activity (Proteus spp., Providencia spp., & Morganella spp.) or no activity (P. aeruginosa spp.).
10.2 Pharmacodynamics
This information is not available for this drug product.
10.3 Pharmacokinetics
The mean pharmacokinetic parameters of tigecycline after single and multiple intravenous doses are summarized in Table 6. Intravenous infusions of tigecycline were administered over approximately 30 to 60 minutes.
Table 6 - Mean (CV%) Pharmacokinetic Parameters of Tigecycline
Single Doses 100 mg | Multiple Dosesa 50 mg q12h | |
|---|---|---|
| Cmax (mcg/mL)b | 1.45 (22%) | 0.87 (27%) |
| Cmax (mcg/mL)c | 0.90 (30%) | 0.63 (15%) |
| AUC (mcg.hr/mL) | 5.19 (36%) |
|
| AUC0-24h (mcg.hr/mL) |
| 4.70 (36%) |
Single Doses 100 mg | Multiple Dosesa 50 mg q12h | |
|---|---|---|
| Cmin (mcg/mL) |
| 0.13 (59%) |
| t1/2 (hr) | 27.1 (53%) | 42.4 (83%) |
| CL (L/h) | 21.8 (40%) | 23.8 (33%) |
| CLr (mL/min) | 38.0 (82%) | 51.0 (58%) |
| Vss (L) | 568 (43%) | 639 (48%) |
a 100 mg initially, followed by 50 mg every 12 hours
b 30-minute infusion
c 60-minute infusion
Absorption:
Tigecycline is administered intravenously and therefore has 100% bioavailability.
Distribution:
The in vitro plasma protein binding of tigecycline ranges from approximately 71% to 89% at concentrations observed in clinical studies (0.1 to 1 .0 mcg/mL). Animal and human pharmacokinetic studies have demonstrated that tigecycline readily distributes to tissues. In rats receiving single or multiple doses of 14C-tigecycline, radioactivity was well distributed to most tissues, with the highest overall exposure observed in bone, bone marrow, thyroid gland, kidney, spleen and salivary gland. In humans, the steady-state volume of distribution of tigecycline averaged 500 to 700 L (7 to 9 L/kg); indicating tigecycline is extensively distributed beyond the plasma volume and into the tissues of humans.
Two studies examined the steady-state pharmacokinetic profile of tigecycline in specific tissues or fluids of healthy subjects receiving tigecycline 100 mg followed by 50 mg every 12 hours. In a bronchoalveolar lavage study, the tigecycline AUC0-12h (134 mcg·hr/mL) in alveolar cells was approximately 77.5-fold higher than the AUC0-12h in the serum of these subjects, and the AUC0-12h (2.28 mcg·hr/mL) in epithelial lining fluid was approximately 32% higher than the AUC0-12h in serum. In a skin blister study, the AUC0-12h (1.61 mcg·hr/mL) of tigecycline in skin blister fluid was approximately 26% lower than the AUC0-12h in the serum of these subjects.
In a single-dose study, tigecycline 100 mg was administered to subjects prior to undergoing elective surgery or medical procedure for tissue extraction. Tissue concentrations at 4 hours after tigecycline administration were measured in the following tissue and fluid samples: gallbladder, lung, colon, synovial fluid and bone. Tigecycline attained higher concentrations in tissues versus serum in gallbladder (38-fold, n=6), lung (8.6-fold, n=1), and colon (2.1-fold, n=5). The concentration of tigecycline in these tissues after multiple doses has not been studied.
Metabolism:
Tigecycline is not extensively metabolized. In vitro studies with tigecycline using human liver microsomes, liver slices, and hepatocytes led to the formation of only trace amounts of metabolites. In healthy male volunteers, receiving 14C-tigecycline, tigecycline was the primary 14C-labeled material recovered in urine and feces, but a glucuronide, an N-acetyl metabolite and a tigecycline epimer (each at no more than 10% of the administered dose) were also present.
Elimination:
The recovery of total radioactivity in feces and urine following administration of 14C-tigecycline indicates that 59% of the dose is eliminated by biliary/fecal excretion, and 33% is excreted in urine. Overall, the primary route of elimination for tigecycline is biliary excretion of unchanged tigecycline. Glucuronidation and renal excretion of unchanged tigecycline are secondary routes.
Tigecycline is a substrate of P-gp based on an in vitro study using a cell line overexpressing P-gp. The potential contribution of P-gp-mediated transport to the in vivo disposition of tigecycline is not known.
Special Populations and Conditions:
Pediatrics: Tigecycline pharmacokinetics was investigated in two studies. No loading dose was administered in these studies. In a single dose study in children aged 8 to 16 years (n=24) tigecycline (0.5, 1, or 2 mg/kg to a maximum dose of 50, 100, or 150 mg, respectively) was administered intravenously over 30 minutes under fed conditions. Two out of six children aged 8 to 11 years receiving a dose of 1 mg/kg vomited therefore the 2 mg/kg dose was not evaluated in this age group. The study showed that for children aged 12 to 16 years (n=16) a dose of 50 mg every 12 hours would likely result in drug exposures comparable to those observed in adults. Large variability was observed in children aged 8 to 11 years of age (n = 8).
In a subsequent dose-finding study, children aged 8 to 11 years of age with cIAI, cSSSI, or CAP received multiple doses of tigecycline (0.75 mg/kg, 1 mg/kg, or 1.25 mg/kg up to a maximum dose of 50 mg) every 12 hours intravenously over 30 minutes. Simulations of the AUC0-24h using clearance values from participating children indicated a 1.2 mg/kg dose (to a maximum of 50 mg) every 12 hours would likely result in exposures comparable to those observed in adults with the approved dosing regimen. Higher incidence of treatment-emergent adverse reactions, i.e., nausea 48.3% and vomiting 46.6% were reported in children as compared with adverse reactions reported from clinical studies in adults, i.e, (nausea 21% and vomiting 13%).
Geriatrics: No overall differences in pharmacokinetics were observed between healthy elderly subjects (n=15, age 65 to 75; n=13, age >75) and younger subjects (n=18)
- receiving a single 100-mg dose of tigecycline. Therefore, no dosage adjustment is necessary based on age. See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics.
- Sex: In a pooled analysis of 38 women and 298 men participating in clinical pharmacology studies, there was no significant difference in the mean (±SD) tigecycline clearance between women (20.7±6.5 L/h) and men (22.8±8.7 L/h). Therefore, no dosage adjustment is necessary based on sex.
- Ethnic Origin: In a pooled analysis of 73 Asian subjects, 53 black subjects, 15 Hispanic subjects, 190 white subjects, and 3 subjects classified as “other” participating in clinical pharmacology studies, there was no significant difference in the mean (±SD) tigecycline clearance among the Asian subjects (22.8±8.8 L/h), black subjects (23.0±7.8 L/h), Hispanic subjects (24.3±6.5 L/h), white subjects (22.1±8.9 L/h), and “other” subjects (25.0±4.8 L/h). Therefore, no dosage adjustment is necessary based on ethnic origin.
- Hepatic Insufficiency: In a study comparing 10 patients with mild hepatic impairment (Child-Pugh A), 10 patients with moderate hepatic impairment (Child-Pugh B), and 5 patients with severe hepatic impairment to 23 age and weight matched healthy control subjects, the single-dose pharmacokinetic disposition of tigecycline was not altered in patients with mild hepatic impairment. However, systemic clearance of tigecycline was reduced by 25% and the half-life of tigecycline was prolonged by 23% in patients with moderate hepatic impairment (Child-Pugh B). In addition, systemic clearance of tigecycline was reduced by 55%, and the half-life of tigecycline is prolonged by 43% in patients with severe hepatic impairment (Child-Pugh C). Based on the pharmacokinetic profile of tigecycline, no dosage adjustment is warranted in patients with mild to moderate hepatic impairment (Child Pugh A and Child Pugh B). However, in patients with severe hepatic impairment (Child Pugh C), the dose of tigecycline should be reduced to 100 mg followed by 25 mg every 12 hours. Patients with severe hepatic impairment (Child Pugh C) should be treated with caution and monitored for treatment response. See 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
- Renal Insufficiency: A single dose study compared 6 subjects with severe renal impairment (creatinine clearance ≤30 mL/min), 4 end stage renal disease patients receiving tigecycline 2 hours before hemodialysis, 4 end stage renal disease patients receiving tigecycline after hemodialysis, and 6 healthy control subjects. The pharmacokinetic profile of tigecycline was not altered in any of the renally impaired patient groups nor was tigecycline removed by hemodialysis. No dosage adjustment of tigecycline is necessary in patients with renal impairment or in patients undergoing hemodialysis. See 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
Cardiovascular: The results from phase 3 studies involving ECGs from 773 subjects showed that the median changes from baseline for QTc(F) and QTc(L) were 6.0 and 3.3 msec, respectively, with an upper bound of a 2-sided 95% CI of 7 and 5 msec, respectively. Comparable median change values from subjects treated with comparator agents (n=788) were 3.0 and 1.2 msec, with upper bounds of the 95% CI of 5 and 3 msec, respectively. Categorical analyses of QTc(F) and QTc(L) changes ≥ 60 msec from baseline occurred, respectively, in 1.8% and 1.3% of tigecycline-treated subjects and in 0.8% and 0.6% of comparator subjects. The differences between the tigecycline and comparator groups were statistically significant for the QTc(F) analysis. QTc(F) and QTc(L) absolute values > 500 msec occurred in 0.4% of tigecycline-treated subjects and in none of the comparator subjects. These differences between the tigecycline and comparator groups were not statistically significant. Although an effect on cardiac repolarization following administration of tigecycline cannot be absolutely excluded, the overall median changes from baseline in the phase 3 studies were generally small, with the upper bounds of the 95% CI ≤10 msec, without associated drug-related adverse cardiac events being reported in concert with any significant changes in QTc.
No significant effect of a single intravenous dose of tigecycline 50 mg or 200 mg on QTc interval was detected in a randomized, placebo- and active-controlled four-arm crossover thorough QTc study of 46 healthy subjects.
11 STORAGE, STABILITY AND DISPOSAL
Prior to reconstitution, TIGECYCLINE (tigecycline) lyophilized powder should be stored at a controlled room temperature 20°C - 25°C, excursions permitted to 15°C to 30°C for up to the expiration date specified on the label. Once reconstituted, TIGECYCLINE may be stored at room temperature (not to exceed 25°C/77°F) for up to 24 hours (up to 6 hours in the vial and the remaining time in the IV bag). Alternatively, TIGECYCLINE mixed with 0.9% Sodium Chloride Injection, USP, 5% Dextrose Injection USP may be stored refrigerated at 2°C - 8°C (36°F - 46°F) for up to 48 hours following immediate transfer of the reconstituted solution into the IV bag.
If the storage conditions exceed 25°C/77°F after reconstitution, tigecycline should be used immediately.
The reconstituted solution should be yellow to orange in color; if not, the solution should be discarded. Parenteral drug products should be inspected visually for particulate matter and discoloration (e.g., green or black) prior to administration.
Any unused medicinal product should be disposed of in accordance with local requirements.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Tigecycline
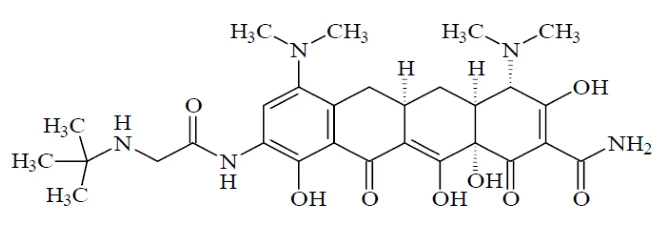
Chemical name: (4S,4aS,5aR,12aS)-9-[2-(tert-butylamino)acetamido]-4,7- bis(dimethylamino)-1,4,4a,5,5a,6,11,12a-octahydro-3,10,12,12a-tetrahydroxy-1,11-dioxo-2-naphthacenecarboxamide
Molecular formula and molecular mass: C29H39N5O8 (585.65 g/mol)
Structural formula:
Physicochemical properties: Tigecycline is an orange powder. The reconstituted solution is yellow to orange, essentially free of particulate matter. Tigecycline is highly ionic and freely soluble throughout the entire pH range of 1 to 14.
pH: The pH of a 1% aqueous solution of Tigecycline is 7.7 to 8.2.
Melting Range: Under hot stage microscopic examination, Tigecycline melts at 165°C to 175°C to form a yellow liquid, which decomposes upon further heating to 185°C.
Partition Coefficient: The n-Octanol/water partition coefficient is 1.338 at pH 8.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Complicated Skin and Skin Structure Infections (cSSSI)
Tigecycline was studied for the treatment of cSSSI in 2 clinical trials.
Patients with complicated deep soft tissue infection including cellulitis (> 10 cm, requiring surgery/drainage or with complicated underlying disease), wound infections, major abscesses, infected ulcers, and burns were enrolled. Patients with severe underlying disease, such as those who were immunocompromised, patients with decubitus ulcer infections, or patients who had infections requiring longer than 14 days of treatment (for example, necrotizing fasciitis), were not enrolled.
Table 7 - Phase 3 Clinical Studies for cSSSI – Study Demographics and Trial Design
| Study No. | Study Design | No. Subjects Randomized | Demography: Sex, Age Range (Mean Age), | IV Dose and Frequency (Duration of Treatment) |
|---|---|---|---|---|
| 3074A1-300-US/CA | Double-blind (third-party unblinded), randomized control comparison study of tigecycline + placebo and vancomycin + aztreonam to treat cSSSI | 583 | 368 M, 205 W 18–92 years (48.9 years) | Tigecycline Arm: 100 mg loading, 50 mg maintenance every 12 hours over 60 minutes (5–14 days) Vancomycin + aztreonam Arm: 1 g vancomycin + 2 g aztreonam every 12 hours (5–14 days) |
| 3074A1-305-WW | Double-blind (third-party unblinded), randomized control comparison study of tigecycline + placebo and vancomycin + aztreonam to treat cSSSI | 546 | 330 M, 213 W 18–88 years (49.4 years) | Tigecycline Arm: 100 mg loading, 50 mg maintenance every 12 hours over 60 minutes (5–14 days) Vancomycin + aztreonam Arm: 1 g vancomycin + 2 g aztreonam every 12 hours (5–14 days) |
The primary efficacy endpoint was the clinical response at the test of cure (TOC window for the final analyses was 12 to 92 days post therapy) visit in the co-primary populations of the clinically evaluable (CE) and clinical modified intent-to-treat (c-mITT) patients. See Table 8. Clinical cure rates at TOC by pathogen in the microbiologically evaluable (ME) patients are presented in Table 9.
Table 8 - Clinical Cureb Rates in cSSSI
Tigecycline n / N (%) | Comparator n / N (%) | 95% CI a | |
|---|---|---|---|
| Integrated | |||
| CE | 365/422 (86.5) | 364/411 (88.6) | -6.8, 2.7 |
| c-mITT | 429/538 (79.7) | 425/519 (81.9) | -7.1, 2.8 |
| Study 300 | |||
| CE | 165/199 (82.9) | 163/198 (82.3) | -7.4, 8.6 |
| c-mITT | 209/277 (75.5) | 200/260 (76.9) | -9.0, 6.1 |
| Study 305 | |||
| CE | 200/223 (89.7) | 201/213 (94.4) | -10.2, 0.8 |
| c-mITT | 220/261 (84.3) | 225/259 (86.9) | -9.0, 3.8 |
a. Confidence Interval (95% CI) were calculated from a generalized linear model with a binomial probability function and an identity link
b. The patient had resolution of all signs and symptoms of the infection (healing of chronic underlying skin ulcer was not required) or improvement to such an extent that no further antibacterial therapy was necessary.
Table 9 - Clinical Cure Rates By Infecting Pathogen in ME Patients with cSSSIa
| Pathogen | Tigecycline n / N (%) | Comparator n / N (%) |
|---|---|---|
| Escherichia coli | 25/29 (86.2) | 26/30 (86.7) |
| Enterobacter cloacae | 7/9 (77.8) | 14/14 (100) |
| Enterococcus faecalis (vancomycin-susceptible only) | 12/16 (75.0) | 19/24 (79.2) |
| Klebsiella pneumoniae | 8/9 (88.9) | 15/16 (93.8) |
| Methicillin-susceptible Staphylococcus aureus (MSSA) | 123/135 (91.1) | 113/120 (94.2) |
| Methicillin-resistant Staphylococcus aureus (MRSA) | 29/37 (78.4) | 26/34 (76.5) |
| Streptococcus agalactiae | 8/8 (100) | 11/13 (84.6) |
| Streptococcus anginosus. | 16/20 (80.0) | 9/10 (90.0) |
| Streptococcus pyogenes | 31/32 (96.9) | 24/27 (88.9) |
| Bacteroides fragilis | 6/8 (75.0) | 4/5 (80.0) |
a. Two cSSSI pivotal studies
Complicated Intra-abdominal Infections (cIAI)
Tigecycline was studied for the treatment of cIAI in 2 clinical trials.
Patients with complicated diagnoses including appendicitis, cholecystitis, diverticulitis, gastric/duodenal perforation, intra-abdominal abscess, perforation of intestine, and peritonitis were enrolled.
Table 10 - Phase 3 Clinical Studies for cIAI – Study Demographics and Trial Design
| Study No. | Study Design | No. Subjects Randomized | Demography: Sex, Age Range (Mean Age) | IV Dose and Frequency (Duration of Treatment) |
|---|---|---|---|---|
| 3074A1-301-WW | Double-blind (third-party unblinded), randomized control comparison study of tigecycline and imipenem/cilastatin to treat cIAI | 834 | 537 M, 288 W 18–91 years (43.6 years) | Tigecycline Arm: 100 mg loading, 50 mg maintenance every 12 hours over 30 minutes (5–14 days) Imipenem/Cilastatin Arm: 500 mg every 6 hours (5-14 days) |
3074A1-306- WW | Double-blind (third-party unblinded), randomized control comparison study of tigecycline and imipenem/cilastatin to treat cIAI | 824 | 479 M, 338 W 18–88 years (48.9 years) | Tigecycline Arm: 100 mg loading, 50 mg maintenance every 12 hours over 30 minutes (5–14 days) Imipenem/Cilastatin Arm: 500 mg every 6 hours (5-14 days) |
The primary efficacy endpoint was the clinical response at the TOC visit (Test of Cure window for the final analyses was 12 to 44 days post therapy) for the co-primary populations of the ME and the microbiologic modified intent to treat (m-mITT) patients. See Table 11. Clinical cure rates at TOC by pathogen in the microbiologically evaluable patients are presented in Table 12.
Table 11 - Clinical Cureb Rates in cIAI
Tigecycline n / N (%) | Comparator n / N (%) | 95% CI a | |
|---|---|---|---|
| Integrated | |||
| ME | 441/512 (86.1) | 442/513 (86.2) | -4.5, 4.4 |
Tigecycline n / N (%) | Comparator n / N (%) | 95% CI a | |
|---|---|---|---|
| m-mITT | 506/631 (80.2) | 514/631 (81.5) | -5.8, 3.2 |
| Study 301 | |||
| ME | 199/247 (80.6) | 210/255 (82.4) | -9.0, 5.4 |
| m-mITT | 227/309 (73.5) | 244/312 (78.2) | -11.8, 2.3 |
| Study 306 | |||
| ME | 242/265 (91.3) | 232/258 (89.9) | -4.0, 6.8 |
| m-mITT | 279/322 (86.6) | 270/319 (84.6) | -3.7, 7.7 |
a. Confidence Interval (95% CI) were calculated from a generalized linear model with a binomial probability function and an identity link
b. The test article and initial intervention (operative and/or radiologically controlled drainage procedure) resolved the intra-abdominal infection. If the patient underwent a percutaneous drainage at baseline, did not respond to treatment within 72 hours of the initial drainage, and underwent an operation and then improved he/she was considered a clinical cure. The patient must not have received additional antibacterial agents during treatment.
Table 12 - Clinical Cure Rates By Infecting Pathogen in ME Patients with cIAIa
| Pathogen | Tigecycline n / N (%) | Comparator n / N (%) |
|---|---|---|
| Citrobacter freundii | 12/16 (75.0) | 3/4 (75.0) |
| Enterobacter cloacae | 14/16 (87.5) | 16/17 (94.1) |
| Escherichia coli | 281/329 (85.4) | 298/343 (86.9) |
| Klebsiella oxytoca | 19/20 (95.0) | 18/20 (90.0) |
| Klebsiella pneumoniae | 46/52 (88.5) | 53/60 (88.3) |
| Enterococcus faecalis (vancomycin susceptible only) | 25/33 (75.8) | 35/47 (74.5) |
| Methicillin-susceptible Staphylococcus aureus (MSSA) | 26/29 (89.7) | 22/24 (91.7) |
| Streptococcus anginosus grpb | 102/120 (85.0) | 61/81 (75.3) |
| Bacteroides fragilis | 67/87 (77.0) | 60/74 (81.1) |
| Bacteroides thetaiotaomicron | 36/41 (87.8) | 31/36 (86.1) |
| Bacteroides uniformis | 12/17 (70.6) | 14/17 (82.4) |
| Bacteroides vulgatus | 14/16 (87.5) | 5/7 (71.4) |
| Clostridium perfringens | 19/20 (95.0) | 20/22 (90.9) |
| Peptostreptococcus micros | 14/18 (77.8) | 9/12 (75.0) |
a. Two cIAI pivotal studies
b. Includes Streptococcus anginosus, Streptococcus intermedius, and Streptococcus constellatus
Community Acquired Pneumonia (CAP) (mild to moderate infections only)
Tigecycline was studied for the treatment of CAP (mild to moderate infections only) in 2 clinical trials.
Patients (18 years of age or older) with CAP who required hospitalization and IV therapy were enrolled in the studies. Patients who required treatment in an intensive care unit, were immunocompromised, or were hospitalized within the 14 days prior to the onset of symptoms or resided in a long-term care facility or nursing home ≥14 days before the onset of symptoms were not enrolled in the studies.
In clinical trials in patients with CAP who required hospitalization and who received at least 1 dose of tigecycline, 20 % had Fine Pneumonia Severity Index scores ≥ IV. Two (2) tigecycline treated patients had a Fine Pneumonia Severity Index score of V. Underlying cardiopulmonary conditions included chronic obstructive pulmonary disease (COPD) in 12 % of patients and congestive heart failure in 7 %. Multilobar disease was noted in 25 % of patients, bilateral disease in 17 %, and pleural effusions in 7 %. S. pneumoniae bacteremia was documented in 6 % of patients.
Table 13 - Phase 3 Clinical Studies for CAP – Study Demographics and Trial Design
| Study No. | Study Design | No. Subjects Randomized | Demography: Sex, Age Range (Mean Age), | IV Dose and Frequency (Duration of Treatment) |
|---|---|---|---|---|
| 3074A1-308-WW | Double-blind (third-party unblinded), randomized active control comparison study of tigecycline and levofloxacin to treat CAP | 418 | 244M, 174 W 18-91years (55 years) | Tigecycline Arm: 100 mg loading, 50 mg maintenance every 12 hours over 30 minutes (7–14 days) Levofloxacin Arm: 500 mg levofloxacin every 24 hours (7-14 days) Switch to oral levofloxacin (500 mg every day) was permitted for both arms after at least 3 days of IV therapy was administered (in-patient) |
| 3074A1-313-WW | Double-blind (third-party unblinded), | 428 | 264 M, 164 W 17-92 years | Tigecycline Arm: |
| Study No. | Study Design | No. Subjects Randomized | Demography: Sex, Age Range (Mean Age), | IV Dose and Frequency (Duration of Treatment) |
|---|---|---|---|---|
| randomized active control comparison study of tigecycline and levofloxacin to treat CAP | (50 years) | 100 mg loading, 50 mg maintenance every 12 hours over 60 minutes (7–14 days) Levofloxacin Arm: 500 mg levofloxacin IV every 12 or 24 hours (7-14 days) | ||
The primary efficacy endpoint was the clinical response at the test of cure (TOC window for the final analyses was 7 to 23 days post therapy) visit in the co-primary populations of the CE and c-mITT patients. See Table 14. Clinical cure rates at TOC by pathogen in the ME patients are presented in Table 15.
Table 14 - Clinical Cureb Rates in CAP
Tigecycline n/N (%) | Comparator n/N (%) | 95% CI a | |
|---|---|---|---|
| Integrated | |||
| CE | 253/282 (89.7) | 252/292 (86.3) | -2.2, 9.1 |
| c-mITT | 319/394 (81.0) | 321/403 (79.7) | -4.5, 7.1 |
| Study 308 | |||
| CE | 125/138 (90.6) | 136/156 (87.2) | -4.4, 11.2 |
| c-mITT | 149/191 (78.0) | 158/203 (77.8) | -8.5, 8.9 |
| Study 313 | |||
| CE | 128/144 (88.9) | 116/136 (85.3) | -5.0, 12.2 |
| c-mITT | 170/203 (83.7) | 163/200 (81.5) | -5.6, 10.1 |
a. Confidence Intervals (95% CI) were calculated from a generalized linear main-effects model including Fine category with a binomial probability function and an identity link.
b. All signs and symptoms of the pneumonia present at the time of enrollment were improved or resolved at TOC. Chest radiographs were improved or no worse. No further antibiotic therapy was necessary for treatment of pneumonia. There was no worsening or appearance of new signs and symptoms of pneumonia.
c. Tigecycline is not indicated for severe CAP.
Table 15 - Clinical Cure Rates By Infecting Pathogen in ME Patients with CAPa
| Pathogen | Tigecycline n/N (%) | Comparator n/N (%) |
|---|---|---|
| Haemophilus influenzae | 14/17 (82.4) | 13/16 (81.3) |
| Streptococcus pneumoniae (penicillin-susceptible only) | 44/46 (95.7) | 39/44 (88.6) |
| Mycoplasma pneumoniae | 37/39 (94.9) | 44/48 (91.7) |
| Chlamydia pneumoniae | 18/19 (94.7) | 26/27 (96.3) |
a . Two CAP pivotal studies
15 MICROBIOLOGY
Tigecycline, a glycylcycline antibiotic, inhibits protein translation in bacteria by binding to the 30S ribosomal subunit and blocking entry of amino-acyl tRNA molecules into the A site of the ribosome. This prevents incorporation of amino acid residues into elongating peptide chains. Tigecycline carries a glycylamido moiety attached to the 9-position of minocycline. The substitution pattern is not present in any naturally occurring or semisynthetic tetracycline and imparts certain microbiologic properties that transcend any known tetracycline-derivative in vitro or in vivo activity. In addition, tigecycline is able to overcome the two major tetracycline resistance mechanisms, ribosomal protection and efflux. However, in recent studies, resistance to Tigecycline, determined by an efflux pump mechanism, mutations in a ribosomal protein, or additional different molecular mechanisms, has been described in Enterobacteriaceae such as Morganella morganii and Proteus mirabilis and other gram-negative microorganisms such as Acinetobacter spp. and Pseudomonas spp. Tigecycline has demonstrated in vitro and in vivo activity against a broad spectrum of bacterial pathogens.
There has been no cross-resistance observed between tigecycline and other antibiotics. In in vitro studies, no antagonism has been observed between tigecycline and other commonly used antibiotics. In general, tigecycline is considered bacteriostatic.
Susceptibility Test Methods
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimum inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure based on dilution methods (broth, agar, or microdilution) or equivalent using standardized inoculum and concentrations of tigecycline. For broth dilution tests for aerobic organisms, MICs must be determined using testing medium that is fresh (<12 hours old). The MIC values should be interpreted according to the criteria provided in Table 16.
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. The standardized procedure requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 15 mcg tigecycline to test the susceptibility of microorganisms to tigecycline. Interpretation involves correlation of the diameter obtained in the disk test with the MIC for tigecycline. Reports from the laboratory providing results of the standard single-disk susceptibility test with a 15 mcg tigecycline disk should be interpreted according to the criteria in Table 16.
Anaerobic Technique
Anaerobic susceptibility testing with tigecycline should be done by the agar dilution method since quality control parameters for broth-dilution are not established.
Table 16 - Susceptibility Test Result Interpretive Criteria for Tigecycline
Minimum Inhibitory Concentrations (mcg/mL) | Disk Diffusion (zone diameters in mm) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Pathogen | S | I | R | S | I | R | ||||||||
Staphylococcus aureus (including methicillin-resistant) | ≤0.5a | - | - | ≥19 | - | - | ||||||||
Streptococcus spp. other than S. pneumoniae | ≤0.25a | - | - | ≥19 | - | - | ||||||||
Streptococcus pneumoniae (penicillin-susceptible isolates only) | ≤0.06a | ≥19 | - | - | ||||||||||
Enterococcus faecalis (vancomycin-susceptible) | ≤0.25a | - | - | ≥19 | - | - | ||||||||
| Enterobacteriaceaeb | ≤2 | 4 | ≥8 | >19 | 15-18 | ≤14 | ||||||||
| Haemophilus influenzae | ≤0.25a | - | - | >19 | - | - | ||||||||
| Anaerobesc | ≤4 | 8 | ≥16 | n/a | n/a | n/a | ||||||||
S= Susceptible; I=Intermediate; R=Resistant
a. The current absence of resistant isolates precludes defining any results other than “susceptible.” Isolates yielding MIC results suggestive of “non-susceptible” category should be submitted to a reference laboratory for further testing.
b. Tigecycline has decreased in vitro activity against Proteus spp., Providencia spp. & Morganella spp.
c. Agar Dilution
A report of “Susceptible” (S) indicates that the pathogen is likely to be inhibited if the antimicrobial compound reaches the concentrations usually achievable. A report of “Intermediate” (I) indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high dosage of drug can be used. This category also provides a buffer zone that prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of “Resistant” (R) indicates that the pathogen is not likely to be inhibited if the antimicrobial compound reaches the concentrations usually achievable; other therapy should be selected.
Quality Control
As with other susceptibility techniques, the use of laboratory control microorganisms is required to control the technical aspects of the laboratory standardized procedures. Standard tigecycline powder should provide the MIC values provided in Table 17. For the diffusion technique using the 15 mcg tigecycline disk, laboratories should use the criteria provided in Table 17 to test quality control strains.
Table 17 - Acceptable Quality Control Ranges for Susceptibility Testing
| QC organism | Minimum Inhibitory Concentrations (mcg/mL) | Disk Diffusion (zone diameters in mm) |
|---|---|---|
| Staphylococcus aureus ATCC 25923 a | Not Applicable | 20-25 |
| Staphylococcus aureus ATCC 29213 | 0.03-0.25 | Not Applicable |
| Escherichia coli ATCC 25922 | 0.03-0.25 | 20-27 |
| Enterococcus faecalis ATCC 29212 | 0.03-0.12 | Not Applicable |
| Streptococcus pneumoniae ATCC 49619 b | 0.016-0.12 | 23-29 |
| Haemophilus influenzae ATCC 49247c | 0.06-0.5 | 23-31 |
| Neisseria gonorrhoeae ATCC 49226 d | Not Applicable | 30-40 |
| Bacteroides fragilis ATCC 25285 e | 0.12-1 | Not Applicable |
| Bacteroides thetaiotaomicron ATCC 29741 e | 0.5-2 | Not Applicable |
| Eubacterium lentum ATCC 43055 e | 0.06-0.5 | Not Applicable |
| Clostridium difficileae ATCC 70057 | 0.12-1 | Not Applicable |
a. ATCC = American Type Culture Collection
b. Testing of S. pneumoniae by broth dilution method should be performed with fresh Mueller-Hinton broth supplemented with 5% lysed horse blood or agar dilution method supplemented with 5% sheep blood and a McFarland 0.5 standard inoculum
c. Testing of H. influenzae should be performed in fresh Haemophilus Test Medium, broth or agar.
d. Testing of N. gonorrhoeae should be performed in GC agar base medium supplemented with 1% defined growth supplement.
e. Testing of anaerobes should be performed by agar dilution only.
The prevalence of acquired resistance may vary geographically and with time for selected species, and local information on resistance is desirable, particularly when treating severe infections. The information in Table 18 and Table 19 provide only approximate guidance on the probability as to whether the micro-organism will be susceptible to tigecycline or not.
A summary of in vitro activities of tigecycline against recent Gram-positive and Gram-negative aerobic clinical isolates performed with reference methods is presented in Table 18 and Table 19 respectively.
Table 18 indicates tigecycline is active against strains of microorganisms both in vitro and in clinical infections. Table 19 indicates in vitro MICs of tigecycline against microorganisms, however the effectiveness of tigecycline in treating clinical indications due to these microorganisms have not been established in adequate and well-controlled studies. Tigecycline has demonstrated decreased in vitro activity against Proteus spp., Providencia spp. & Morganella spp. Pseudomonas aeruginosa is inherently resistant to tigecycline.
Table 18 - In vitro activities of tigecycline against organisms for which tigecycline has demonstrated clinical efficacy
MIC (mcg/mL) | ||||
|---|---|---|---|---|
| Organism | Number of Isolates | Range | 50% | 90% |
| Enterococcus faecalis (VSE) | 159 | 0.03-0.25 | 0.06 | 0.12 |
| Staphylococcus aureus (MSSA) | 160 | 0.03-0.25 | 0.12 | 0.12 |
| Staphylococcus aureus (MRSA) | 165 | 0.03-2 | 0.12 | 0.25 |
| Streptococcus agalactiae | 115 | ≤0.03-0.06 | ≤0.03 | 0.06 |
| Streptococcus pneumoniae (penicillin-susceptible isolates) | 189 | 0.004-0.25 | 0.015 | 0.06 |
| Streptococcus pyogenes | 176 | ≤0.03-0.06 | ≤0.03 | 0.06 |
| Citrobacter freundii | 160 | 0.03-8 | 0.25 | 0.5 |
| Enterobacter cloacae | 160 | 0.25-8 | 0.5 | 0.5 |
| Escherichia coli | 208 | 0.06-1 | 0.12 | 0.5 |
| Haemophilus influenzae | 204 | 0.06-1 | 0.25 | 0.5 |
| Klebsiella pneumoniae | 180 | 0.25-4 | 0.5 | 1 |
| Clostridium perfringens a | 89 | ≤0.06-16 | 0.5 | 2 |
| Peptostreptococcus micros a | 53 | ≤0.06-0.25 | ≤0.06 | ≤0.06 |
MIC (mcg/mL) | ||||
|---|---|---|---|---|
| Organism | Number of Isolates | Range | 50% | 90% |
| Bacteroides fragilis a | 943 | ≤0.06-32 | 1 | 8 |
| Bacteroides thetaiotaomicron a | 451 | ≤0.06-32 | 1 | 8 |
| Bacteroides uniformis a | 134 | ≤0.06-16 | 0.5 | 4 |
| Bacteroides vulgatus a | 159 | ≤0.06-8 | 1 | 4 |
| Chlamydia pneumoniae | 10 | 0.12-0.25 | 0.12 | 0.12 |
| Mycoplasma pneumoniaeb | 30 | 0.06-0.25 | 0.12 | 0.25 |
a. MICs of anaerobic bacteria were determined by agar dilution
b. MICs of M. pneumoniae were determined by agar dilution
Table 19 - In vitro activities of tigecycline against recent clinical isolates performed with reference methods, however clinical efficacy has not yet been demonstrated
MIC (mcg/mL) | ||||
|---|---|---|---|---|
| Organism | Number of Isolates | Range | 50% | 90% |
| Gram-positive aerobes | ||||
| Enterococcus avium | 140 | ≤0.016-0.25 | 0.06 | 0.12 |
| Enterococcus casseliflavus | 100 | 0.03-0.25 | 0.06 | 0.12 |
| Enterococcus faecalis (VRE) | 147 | ≤0.016-0.5 | 0.06 | 0.12 |
| Enterococcus faecium (VSE) | 171 | ≤0.03-0.5 | 0.06 | 0.12 |
| Enterococcus faecium (VRE) | 155 | ≤0.03-0.25 | ≤0.03 | 0.12 |
| Enterococcus gallinarium | 164 | ≤0.03-0.25 | 0.06 | 0.12 |
| Staphylococcus epidermidis (MSSE) | 159 | 0.03-2 | 0.12 | 0.5 |
| Staphylococcus epidermidis (MRSE) | 155 | 0.03-1 | 0.12 | 0.5 |
| Staphylococcus haemolyticus | 166 | ≤0.016-2 | 0.25 | 0.5 |
| Streptococcus pneumoniae (penicillin-resistant isolates) | 269 | ≤0.03-0.25 | ≤0.03 | 0.06 |
| Listeria monocytogenes | 220 | ≤0.03-0.12 | 0.06 | 0.12 |
| Gram-negative aerobes | ||||
| Citrobacter koseri (C. diversus) | 175 | 0.06-2 | 0.25 | 0.5 |
| Enterobacter aerogenes | 161 | 0.03-4 | 0.25 | 1 |
| Haemophilus parainfluenzae | 166 | 0.06-2 | 0.5 | 1 |
| Klebsiella oxytoca | 140 | 0.12-2 | 0.25 | 0.5 |
MIC (mcg/mL) | ||||
|---|---|---|---|---|
| Organism | Number of Isolates | Range | 50% | 90% |
| Legionella pneumophilaa | 50 | 2-8 | 4 | 8 |
| Moraxella catarrhalis | 240 | ≤0.03-0.25 | 0.06 | 0.12 |
| Morganella morganii b | 145 | 0.12-8 | 1 | 4 |
| Neisseria meningitidis | 298 | ≤0.03-0.5 | ≤0.03 | 0.12 |
| Proteus mirabilis b | 160 | 0.5-16 | 4 | 8 |
| Proteus vulgaris b | 220 | 0.5-8 | 2 | 4 |
| Providencia stuartii b | 232 | 0.12-64 | 2 | 4 |
| Providencia rettgeri b | 192 | 0.12-16 | 2 | 4 |
| Salmonella enterica ser. Enteritidis | 299 | 0.12-2 | 0.5 | 1 |
| Salmonella enterica ser. Paratyphi | 261 | 0.12-2 | 0.5 | 0.5 |
| Salmonella enterica ser. Typhimurium | 269 | 0.12-2 | 0.5 | 1 |
| Salmonella enterica ser. Typhi | 304 | 0.06-1 | 0.25 | 0.5 |
| Serratia marcescens | 160 | 0.25-8 | 1 | 2 |
| Acinetobacter baumannii | 158 | 0.03-4 | 0.5 | 2 |
| Aeromonas hydrophila | 142 | 0.06-1 | 0.25 | 0.5 |
| Pasteurella multocida | 126 | ≤0.03-0.25 | ≤0.03 | 0.12 |
| Pseudomonas aeruginosa c | 160 | 0.25-32 | 8 | 16 |
| Stenotrophomonas maltophilia | 160 | 0.06-16 | 0.5 | 2 |
| Gram-positive anaerobes | ||||
| Peptostreptococcus spp. d | 84 | ≤0.06-2 | ≤0.06 | 0.25 |
| Eubacterium lentum d | 48 | <0.06-1 | 0.25 | 0.5 |
| Propionibacterium spp. d | 44 | <0.06-0.5 | <0.06 | 0.5 |
| Gram-negative anaerobes | ||||
| B. fragilis group d | 46 | ≤0.06-16 | 0.5 | 2 |
| Bacteroides caccae d | 98 | 0.5-64 | 1 | 8 |
| Bacteroides distasonis d | 161 | 0.12-16 | 2 | 8 |
| Bacteroides ovatus d | 162 | 0.03-32 | 1 | 8 |
| Prevotella spp. d | 108 | 0.015-5 | 0.25 | 0.5 |
| Nontuberculous Mycobacteria spp. | ||||
| M. abscessus | 38 | ≤ 0.06-1 | ≤ 0.12 | 0.25 |
| M. chelonae | 48 | ≤ 0.06 - ≤ 0.25 | ≤ 0.06 | < 0.12 |
| M. fortuitum | 36 | ≤ 0.06 - ≤ 0.25 | ≤ 0.06 | < 0.12 |
a Tigecycline is inactivated by the testing medium required to grow Legionella
b Tigecycline has decreased in vitro activity against Proteus spp., Morganella spp. and Providencia spp.
c. No significant in vitro activity against P. aeruginosa has been demonstrated.
d. MICs of anaerobic bacteria were determined by agar dilution
16 NON-CLINICAL TOXICOLOGY
General Toxicology: The toxicity of tigecycline administered IV was evaluated in single-dose studies in mice and rats, tolerability/pilot studies in rats, rabbits, dogs, and monkeys, and repeat-dose (2-week, 2-week with 3-week recovery, and 13-week) studies in rats and dogs; the 2-week and 13-week studies also evaluated toxicokinetics. Special toxicity studies with tigecycline were conducted that assessed the following: hematotoxicity recoverability in dogs; phototoxicity in rats; emetogenic potential in the shrew; antigenicity in guinea pigs, mice and rats; in vitro blood compatibility in rat, dog, and human blood; and cellular and mitochondrial protein synthesis in rat and dog hepatocytes. Genotoxic potential was evaluated in mammalian in vitro and in vivo assays, but not in bacterial reverse mutation assays due to the antibacterial action of tigecycline. Cross-sensitization with structurally-related tetracyclines has not been evaluated. Functional immunotoxicity has not been evaluated.
The toxicities of the human metabolites (tigecycline glucuronide and N-acetyl 9-aminominocycline) have not been evaluated following the administration of tigecycline.
Bolus intravenous administration of tigecycline has been associated with clinical observations consistent with histamine release in both the rat and dog species (edema, erythema, itching, labored breathing, red pigmentation around the eyes, nose, and mouth, salivation, swollen areas {muzzle, paws, pinnae, peri-orbital region}). These effects were observed predominantly at dosages ≥ 20 mg/kg/day in rats and ≥ 5 mg/kg/day in dogs, corresponding to animal:human exposure ratio (ER) 14.3 and 2.8 , based on AUC. Serum histamine levels were elevated at between 5 to 20 minutes post-dose in the dog, but not the rat. Other possible histamine-related changes included lacrimation, vocalization, emesis, and fecal changes.
The observed decreases in total protein, albumin, and globulin might be attributed in part to an inhibition of mitochondrial protein synthesis in mammalian cells. The results of an exploratory in vitro study suggest that high concentrations of tigecycline (≥ 10 mcg/mL) may inhibit mitochondrial protein synthesis in vivo.
Yellow discoloration of bone was observed in the 2- and 13-week studies in rats at ≥ 42.3 and 6 mg/kg/day, respectively.
In rats, injection site lesions were observed at tigecycline concentrations ≥ 25 mg/mL in the 2-week studies (dosages of 30 and 70 mg/kg/day) and at tigecycline concentrations ≥ 3 mg/mL in the 13-week study (dosages of 6 and 20 mg/kg/day). These effects were considered to result from the repeated injection of tigecycline into a small vessel.
Toxicologically significant erythrocyte, reticulocyte, platelet, and/or leukocyte decreases without histopathologic bone marrow correlates were seen in the 13-week rat study at ≥ 6 mg/kg/day, corresponding to ERs of 3.3 (male) and 2.4 (female) based on AUC, and in a 2-week dog study at ≥ 5 mg/kg/day (ER of 2.8, based on AUC). Histopathologic correlates in the bone marrow to the hematologic changes were observed at ≥ 30 mg/kg/day in the 2-week rat study and at ≥ 12 mg/kg/day in the 2-week dog study, corresponding to ERs ≥ 8.2 and ≥ 9.8, respectively. Decreased leukocytes was seen in rats at 5 mg/kg/day (ER of 1.2, based on AUC), but was not considered toxicologically significant due to the small magnitude of change. These hematologic alterations were shown to be reversible within a 3-week recovery period after 2 weeks of dosing.
No evidence of photosensitivity was observed in rats following administration of tigecycline.
Carcinogenicity: Lifetime studies in animals have not been performed to evaluate the carcinogenic potential of tigecycline.
Mutagenicity: No mutagenic or clastogenic potential was found. Tigecycline was not genotoxic in 4 in vitro assays (chromosome aberration assay in CHO cells, forward mutation assay in CHO cells, and 2 forward mutation assays in mouse lymphoma cells) and 1 in vivo assay (mouse micronucleus). The genotoxic potential of elevated levels of tigecycline drug product impurities was not evaluated.
Reproductive and Developmental Toxicology:
Reproduction Toxicity: Tigecycline did not affect mating, fertility, ovaries, or estrous cycles in rats at up to 12 mg/kg/day (ER of 4.7 based on AUC).
Results from animal studies using 14C-labeled tigecycline indicate that tigecycline is excreted readily via milk of lactating rats. Consistent with the limited oral bioavailability of tigecycline there was little or no systemic exposure to tigecycline in nursing pups as a result of exposure via maternal milk.
Developmental Toxicity: Tigecycline was not teratogenic in the rat or rabbit. In preclinical safety studies in the rat, 14C-labeled tigecycline crossed the placenta and was found in fetal tissues, including fetal bony structures. The administration of tigecycline was associated with slight reductions in fetal weights in mice at 5 mg/kg/day, in rats at 12 mg/kg/day (ER of 4.7, based on AUC) and in rabbits at 4 mg/kg/day (ER of 1.1, based on AUC). An increased incidence of minor skeletal anomalies (delays in bone ossification) occurred in rats at 4 mg/kg/day (ER of 1.8, based on AUC) and in rabbits, together with an increased incidence of fetal loss, at 4 mg/kg/day (ER of 1.1, based on AUC), a dosage producing minimal maternal toxicity.
The overall animal:human exposure ratios, based on AUC0-24, in the 13-week general toxicity studies at the NTEL for rats (2 mg/kg/day) was 1.0 and at the NOAEL (1.5 mg/kg/day) for dogs was 0.7. Human exposure data were projected based on a steady state AUC0-12 (50 mg q12h) of 3.07 mcg•h/mL, which is equivalent to an AUC0-24 of 6.1 mcg•h/mL (total daily dose of 100 mg).
Table 20 - Toxicology Study Overview
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| Single-Dose GTR-31860 | Mice; CD-1; 3/sex/dosage; 43 – 46 days; 30 - 34 g (males), 22 – 25 g (females) | IV, bolus (needle); 1 day |
87.5 mg/kg (35 mg/mL), 175 mg/kg (35 mg/mL); 2.5 – 5 mL/kg; pH of the dosing solution was 8.1 |
| ||||
| Single-Dose GTR-31861 | Rats; S-D; 3/sex/dosage; 43 – 46 days; 186 – 241 g (males), 159 – 182 g (females) | IV, bolus (needle); 1 day | 75 mg/kg (15 mg/mL), 150 mg/kg (60 mg/mL), 300 mg/kg (60 mg/mL); 2.5 – 5 mL/kg; pH of the dosing solutions ranged from 8.0 to 8.1 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Repeat-Dose MIRACL-26228 | Rats; S-D; 6M/dosage; for TK, 6 and 4 M at 42.3 and 84.7 mg/kg/day; ~ 9 weeks; 269 – 334 g | IV, two 1-h infusions, 8 h apart (catheter); twice daily for 14 days | 42.3e (2.25 mg/mL), 84.7e (4.5 mg/mL), 169e (9 mg/mL); 0.17 mL/kg/min for 60 minutes |
|
Repeat-Dose GTR-31608 | Rats; S-D; 15/sex/dosage; for TK: 9M/dosage, 9F at 30 mg/kg/day; ~ 7 weeks; 219 - 275 g (males), 153 – 199 g (females) | IV, bolus (needle); once daily for 14 or 15 days | 0 (0 mg/mL), 5 (5 mg/mL),f 30 (30 mg/mL), 70 (70 mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 7.9 to 8.1 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Repeat-Dose GTR-31608 (con’t) |
| |||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| ||||
Repeat-Dose RPT-42195 Repeat-Dose | Rats; S-D; 15/sex/dosage, 5/sex/dosage retained for recovery; ~ 6 weeks; 263 – 301 g (males), 162 – 207 g (females) | IV, bolus (needle); once daily for 14 days, with 3-week recovery | 0 (0 mg/mL), 20 (10 mg/mL), 50 (25 mg/mL), 70 (35 mg/mL); 2 mL/kg; pH of the dosing solutions ranged from 7.81 to 7.90 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| RPT-42195 (cont’d) |
| |||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Repeat-Dose RPT-42195 (cont’d) |
| |||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| ||||
Repeat-Dose RPT-41074 | Rats; S-D; 15/sex/dosage; for TK, 21 males at 2 and 20 mg/kg/day, 21/sex at 6 mg/kg/day; ~ 6 weeks; 177 – 214 g | IV, bolus (needle); once daily for 13 weeks | 0 (0 mg/mL), 2 (1 mg/mL), 6 (3 mg/mL), 20 (10 mg/mL); 2 mL/kg; pH of the dosing solutions ranged from 7.71 to 7.96 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
(males), 138 – 168 g (females) |
| |||
Repeat-Dose Pilot GTR-30663 | Dogs; Beagle; 2/sex/dosage; ~5 – 6 months; 6.5 – 9.0 kg | IV, bolus (needle); once daily for 14 days | 0 (0 mg/mL), 2 (5 mg/mL), 5 (5 mg/mL), 12 (5 mg/mL); |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
0.4, 1.0, or 2.4 mL/kg |
AUC 0-∞ (mcg•h/mL): 6.08, 12.3, 34. | |||
Repeat-Dose Pivotal GTR-31609 | Dogs; Beagle; 3/sex/dosage; ~7.5 months; 10.0 – 11.0 kg (males), 7.8 – 10.7 kg (females) | IV, bolus (needle); once daily for 14 or 15 days | 0 (0 mg/mL), 2 (1 mg/mL), 5 (2.5 mg/mL), 12 (6 mg/mL), 20 (10 mg/mL); 2 mL/kg; pH of dosing solutions ranged from 7.9 to 8.0 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Repeat-Dose Pivotal GTR-31609 (cont’d) |
| |||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| ||||
Repeat-Dose Pivotal RPT-42488 | Dogs; Beagle; 6/sex/dosage, 3/sex/dosage retained for recovery; ~ 6 – 7 months; 9.0 – 12.1 kg (males), 5.8 – 9.8 kg (females) | IV, bolus (needle); once daily for 14 days, 3-week recovery | 0 (0 mg/mL), 5 (5 mg/mL), 12 (12 mg/mL); 1 mL/kg; pH of dosing solutions ranged from 7.79 to 7.88 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Repeat-Dose Pivotal RPT-42488 (cont’d) |
| |||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| ||||
Repeat-Dose Pivotal RPT-41664 Repeat-Dose Pivotal RPT-41664 (cont’d) | Dogs; Beagle; 3/sex/dosage; ~ 6
7.2 – 8.7 kg (males), 6.2 – 7.5 kg (females) | IV, bolus (needle); once daily for 13 weeks | 0 (0 mg/mL), 0.5 (0.5 mg/mL), 1.5 (1.5 mg/mL), 5 (5 mg/mL); 1 mL/kg; pH of dosing solutions ranged from 7.60 to 7.89 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| Genotoxicity | ||||
| Forward Mutation Assay | CHO Cells | In Vitro | 25 to 2000 mcg/mL; NA |
|
| Forward Mutation Assay | Mouse Lymphoma Cells | In Vitro | 6.25 to 500 mcg/mL; NA |
|
| Forward Mutation Assay | Mouse Lymphoma Cells | In Vitro | 6.25 to 400 mcg/mL; NA |
|
Chromosome Aberration | CHO Cells | In Vitro | 0.291 to 1000 mcg/mL; NA |
|
Micronucleus Assay | Mice; CD-1 Bone Marrow Cells | IV | 37.5, 75, 150; single dose |
|
| Reproductive Toxicity | ||||
Dose-Ranging Fertility and Developmental Toxicity GTR-32617 | Rats; S-D; 10/sex/dosage; 10 – 12 weeks; 358 – 414 g (males), 198 - 268 g (females) | IV, bolus (needle); M: once daily for 4 weeks prior to cohabitation and continuing throughout cohabitation, F: once daily 2 weeks prior to | 0 (0 mg/mL), 5 (5 mg/mL), 15 (15 mg/mL), 45/30 (45/30mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 7.8 to 8.0 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Dose-Ranging Fertility and Developmental Toxicity GTR-32617 (cont’d) | cohabitation, continuing throughout cohabitation, and through GD 16 |
| ||
Fertility and Developmental Toxicity RPT-42298 | Rats; S-D; 25/sex/dosage, 21F/dosage for TK; 47 – 51 days (males). 68 – 72 days (females); 233 – 289 g (males), 189 – 260 g (females) | IV, bolus (needle); M: once daily for 10 weeks prior to cohabitation, and until 1 day prior to necropsy, F: once daily for 2 weeks prior to | 0 (0 mg/mL), 1 (1 mg/mL), 4 (4 mg/mL), 12 (12 mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 7.74 to 7.94 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Fertility and Developmental Toxicity RPT-42298 (cont’d) | cohabitation and through GD 17 |
| ||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
GD 17: C5min (mcg/mL): 1.78, 10.7, 24.0 AUC0-24 (mcg•h/mL): 2.30, 11.3, 28.5. | ||||
Perinatal/ Postnatal Toxicity RPT-53525 | Rats; S-D; 25F/dosage; 11 weeks; 235 – 296 g | IV, bolus (needle); once daily from GD 6 through day 20 postpartum | 0 (0 mg/mL), 1 (1 mg/mL), 4 (4 mg/mL), 12 (12 mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 6.68 to 7.95 |
|
Dose-Ranging Developmental Toxicity GTR-33215 | Rabbits; NZW 8F/dosage, 4F/dosage for TK; 5 - 6 months; 2.9 – 4.1 kg; | IV, bolus (needle); once daily from GD 6 through GD 18 | 0 (0 mg/mL), 1 (1 mg/mL), 4 (4 mg/mL), 16 (16 mg/mL); 1 mL/kg; |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Dose-Ranging Developmental Toxicity GTR-33215 (cont’d) | pH of the dosing solutions ranged from 7.9 to 8.0 |
| ||
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
| ||||
Developmental Toxicity RPT-42304 | Rabbits; NZW 20F/dosage; ~ 5 months; 3.0 – 3.5 kg | IV, bolus (needle); once daily from GD 6 through GD 18 | 0 (0 mg/mL), 0.25 (0.25 mg/mL), 1 (1 mg/mL), 4 (4 mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 7.53 to 7.97 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Developmental Toxicity RPT-42304 (cont’d) |
| |||
| Other Toxicity Studies | ||||
Antigenicity GTR-33263 | Sensitization: Mice; BALB/c and C3H/He; 6F/strain/dose group | IV, bolus (needle) or IP; once a week for 3 weeks | 0 (0 mg/mL), 3 (3 mg/mL), 30 (30 mg/mL); 10 mL/kg; pH of the dosing |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
7 – 9 weeks; 14 – 22 g Challenge: Rats; S-D 2F/serum sample, 6F; 10 weeks; 177- 253 g | IV, bolus; 1 day | solutions ranged from 7.18 to 8.29 30; 1 mL/kg |
| |
Antigenicity GTR-33124 | Guinea Pig; Hartley; 4M/group 5 weeks; 299 – 455 g | IV, bolus (needle) or SC; 1 day | 0.3 (0,3 mg/mL), 1 (1 mg/mL), 3 (3 mg/mL); 1 mL/kg; pH of the dosing solutions ranged from 7.15 to 7.81 |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Hematotoxicity Recoverability GTR-33279 | Dogs; Beagle 3/sex/dosage; ~ 11 months; 9.3 – 11.8 kg (males), 7.7 – 12.3 kg (females) | IV, bolus (needle); once daily for 2 weeks with a 3-week recovery | 0 (0 mg/mL), 12 (6 mg/mL); 2 mL/kg; pH of the dosing solution ranged from 7.0 to 8.0 |
|
Phototoxicity Assessment RPT-55059 | Male Rats; Long-Evans; 5M/dosage; ~ 8 weeks; 263 – 284 g | IV, bolus (needle); single dose UVR exposure: 30 min (½ MED) | 0 (0 mg/mL), 10 (10 mg/mL), 30 (30 mg/mL), 70 (70 mg/mL); 1 mL/kg; pH of the dosing |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
to eyes and skin at 5 and 120 minutes post-dose | solutions ranged from 7.8 to 7.9 |
| ||
Emetogenic Potential RPT-39987 | Suncus murinus; 2, 3, or 4/dosage Suncus murinus; 3/dosage | IV, infusion (catheter); single dose Oral; single dose | 0, 100, 300, 600; 10 mL/kg; 1 mL/min; 0, 300, 600, 1000; 10 mL/kg; distilled water |
|
In Vitro Blood Compatibility GTR-32502 | Rat, Dog, and Human Blood | In Vitro | 70 mg/mL (rat) 20 mg/mL (dog) 8 mg/mL (human); NA |
|
Cellular Protein Synthesis and | Dog Hepatocytes | In Vitro | 1 to 100 mcg/mL; 20 hours |
|
| Type of Study | Species; Strainb; N; Age; Weight | Routec; Duration | Dosagea (Concentration); Dosing Volume or Infusion Rate; Vehicled | Principal Effects Observed |
|---|---|---|---|---|
Mitochondrial Protein Synthesis MIRACL-26519 | Rat and Dog Mitochondrial Suspensions | 9.4 to 282 mcg/mL; 1 hour |
| |
a. Dosage in mg/kg/day for repeat-dose studies, as appropriate, unless otherwise indicated.
b. Includes males and females unless otherwise indicated.
c. IV bolus unless otherwise indicated.
d. The vehicle was 0.9% saline, unless otherwise noted.
e. Dosages are expressed in the report as 45, 90, or 180 mg/kg/day of the monohydrochloride salt of tigecycline.
f. The NTEL is underlined for the 2- and 13-week pivotal studies in rats, 2-week pivotal study in dogs, and 13-week pivotal study in dogs (also NOAEL).
Note:
In the studies summarized in Table 20, tigecycline was administered as the free base, as the monohydrochloride salt, or as the dihydrochloride salt. Unless otherwise noted in the table, the approximate pH of the dosing solution was not tested
ALT = Alanine aminotransferase; AUC = Area under the concentration-versus-time curve; BUN = Blood urea nitrogen; CD = Cesarean-derived; CHO = Chinese hamster ovary; F = Females, F0 = Parental; GD = Gestation day; GI = Gastrointestinal; IP = Intraperitoneal; IV = Intravenous; LD50 = Median lethal dosage; M = Males, MPV = Mean platelet volume; NA = Not applicable; NOAEL = No-observed-adverse-effect level; NTEL = No-toxicologic-effect level; NZW = New Zealand White; RBC = Red blood cell; SC = Subcutaneous; S-D = Sprague-Dawley; TK = Toxicokinetics; WBC = White blood cell.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. TYGACIL® (Tigecycline for Injection, 50 mg/vial), submission control 272000, Product Monograph, Pfizer Canada ULC. (JUL 04, 2023)