


Product Monograph - Tranexamic Acid Injection (Auro Pharma)
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 01/2023 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | 01/2023 |
| 7 WARNINGS AND PRECAUTIONS | 01/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 3
1 INDICATIONS ...................................................................................................................... 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 CONTRAINDICATIONS ......................................................................................................... 4
4 DOSAGE AND ADMINISTRATION......................................................................................... 4
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.3 Reconstitution ...................................................................................................... 5
4.4 Administration ...................................................................................................... 6
5 OVERDOSAGE ..................................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................................... 7
7 WARNINGS AND PRECAUTIONS .......................................................................................... 8
7.1 Special Populations ..............................................................................................10
7.1.1 Pregnant Women ..............................................................................................10
7.1.2 Breast-feeding...................................................................................................11
7.1.3 Pediatrics ..........................................................................................................11
7.1.4 Geriatrics ..........................................................................................................11
8 ADVERSE REACTIONS .........................................................................................................11
8.1 Adverse Reaction Overview ..................................................................................12
8.2 Clinical Trial Adverse Reactions.............................................................................12
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .......................................................12
8.3 Less Common Clinical Trial Adverse Reactions.......................................................12
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics .................................12
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .............................................................................................12
8.5 Post-Market Adverse Reactions ............................................................................13
9 DRUG INTERACTIONS.........................................................................................................13
9.2 Drug Interactions Overview ..................................................................................13
9.4 Drug-Drug Interactions .........................................................................................13
9.5 Drug-Food Interactions.........................................................................................13
9.6 Drug-Herb Interactions.........................................................................................13
9.7 Drug-Laboratory Test Interactions ........................................................................13
10 CLINICAL PHARMACOLOGY ..............................................................................................14
10.1 Mechanism of Action..........................................................................................14
10.2 Pharmacodynamics ............................................................................................14
10.3 Pharmacokinetics ...............................................................................................15
11 STORAGE, STABILITY AND DISPOSAL ................................................................................16
12 SPECIAL HANDLING INSTRUCTIONS..................................................................................16
PART II: SCIENTIFIC INFORMATION .......................................................................................17
13 PHARMACEUTICAL INFORMATION...................................................................................17
14 CLINICAL TRIALS...............................................................................................................17
14.1 Clinical Trials by Indication..................................................................................17
14.2 Comparative Bioavailability Studies ....................................................................17
14.3 Immunogenicity .................................................................................................17
14.4 Clinical Trials – Reference Biologic Drug ..............................................................17
15 MICROBIOLOGY ...............................................................................................................17
16 NON-CLINICAL TOXICOLOGY ............................................................................................18
17 SUPPORTING PRODUCT MONOGRAPHS...........................................................................19
PATIENT MEDICATION INFORMATION ..................................................................................20
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TRANEXAMIC ACID INJECTION (tranexamic acid) is indicated for:
- Increased local fibrinolysis when the diagnosis is indicative of hyperfibrinolysis, as with dental extraction in patients with coagulopathies (in conjunction with antihaemophilic factor).
1.1 Pediatrics
No data are available to Health Canada for TRANEXAMIC ACID INJECTION for intravenous administration; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Clinical studies of tranexamic acid did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
2 CONTRAINDICATIONS
- Intrathecal and epidural administration of tranexamic acid is contraindicated.
- Patients with a history or risk of thrombosis should not be given TRANEXAMIC ACID INJECTION (tranexamic acid), unless at the same time it is possible to give treatment with anticoagulants. The preparation should not be given to patients with acquired disturbances of colour vision. If disturbances of vision arise during the course of treatment the administration of the preparation should be discontinued.
- Patients with active thromboembolic disease, such as deep vein thrombosis, pulmonary embolism, and cerebral thrombosis.
- Patients with subarachnoid haemorrhage: the limited clinical experience shows that a reduced risk for re-bleeding is offset by an increase in the rate of cerebral ischaemia.
- Haematuria (see 7 WARNINGS and PRECAUTIONS)
- TRANEXAMIC ACID INJECTION is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION ANDPACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- TRANEXAMIC ACID INJECTION is intended for intravenous injection or infusion only.
- Erroneous administration of TRANEXAMIC ACID INJECTION via intrathecal and epidural routes has resulted in serious harm, including death (see 7 WARNINGS AND PRECAUTIONS)
- Tranexamic acid blood levels are increased in patients with renal insufficiency. Dose modifications are required in patients with renal insufficiency (see 4.2 Recommended dose and Dosage Adjustment)
- Hypotension may occur after fast injection.
- The risk for thromboembolic events may be increased in patients using hormonal contraceptives. If TRANEXAMIC ACID INJECTION has to be used in these patients, advise them to use an effective alternative (nonhormonal) contraceptive method. (see 9 DRUG INTERACTIONS).
4.2 Recommended Dose and Dosage Adjustment
- Dental Surgery in Patients with Coagulopathies: 2 hours before the operation, Factor VIII and Factor IX should be given as well as TRANEXAMIC ACID INJECTION, 10 mg/kg body weight intravenously. After the operation the patient does not generally require further substitution therapy.
- Patients with Impaired Renal Function: In patients with serum creatine concentrations of 120 to 250 mcmol/L, the recommended dose is 10 mg/kg intravenously tranexamic acid twice daily. At serum creatine levels of 250 to 500 mcmol/L the dosage should be 10 mg/kg intravenously at 24 hourly intervals, and at serum creatine levels of 500 mcmol/L or more, the same dose should be given at intervals of 48 hours between doses.
4.3 Reconstitution
Parenteral Products:
For intravenous infusion TRANEXAMIC ACID INJECTION may be mixed with:
- electrolyte solutions (e.g. 0.9% NaCl solution, Ringer’s solution),
- carbohydrate solutions (e.g. 5% glucose solution),
- amino acid solutions and
- dextran solutions (e.g. dextran 40).
Heparin may be added to TRANEXAMIC ACID INJECTION. TRANEXAMIC ACID INJECTION should not be mixed with blood and infusion solutions containing penicillin.
The required volume of TRANEXAMIC ACID INJECTION may be added to the chosen infusion solution to achieve final concentrations of 1 or 2 g in 100 mL (10 or 20 mg/mL, 1% or 2%). A solution with a 100 mL final volume would be prepared as shown in the table 1.
Table 1 - Reconstitution
| Ampoules Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Concentration per mL |
| 5 mL | qsp 100 mL | 100 mL | Solution 0.5 % (5 mg / mL) |
| 10 mL | qsp 100 mL | 100 mL | Solution 1 % (10 mg / mL) |
| 2 x 10 mL | qsp 100 mL | 100 mL | Solution 2 % (20 mg / mL) |
* See above for compatible diluents. NB:
1g of tranexamic acid is obtained from 1 ampoule of 10 mL or 2 ampoules of 5 mL;
2g of tranexamic acid are obtained from 2 ampoules of 10 mL or 4 ampoules of 5 mL;
1g of tranexamic acid is obtained from 1 vial of 10 mL or 2 vials of 5 mL;
2g of tranexamic acid are obtained from 2 vials of 10 mL or 4 vials of 5 mL.
An example of preparation and administration of a solution for intravenous infusion is summarized in the table 2.
| Table 2: Infusion rates for undiluted and diluted tranexamic acid solutions | ||||||||
| Weight (kg) | Bolus (50 mg/min) | |||||||
| Undiluted solution (100 mg/mL) | Diluted solution | |||||||
| 1% (10 mg/mL) | 2% (20 mg/mL) | |||||||
| Infusion rate | - | 0.5 mL/min | 5 mL/min | 2.5 mL/min | ||||
| Example of a patient dosed at 10 mg/kg | 70 | 7mL (14 mins) | 70 mL (14 mins) | 35 mL (14 mins) | ||||
The mixture should be used immediately after preparation. If storage is necessary, the mixture should be stored at 2 – 8oC for a maximum of 24 hours. Mixture not used within 24 hours of preparation, should be discarded.
The ampoules and vials of TRANEXAMIC ACID INJECTION are sterile. TRANEXAMIC ACID INJECTION is intended for single use. Unused product must be discarded. As with all parenteral drug products, TRANEXAMIC ACID INJECTION should be inspected visually for clarity, particulate matter, precipitation, discolouration and leakage prior to administration, whenever solution and container permit.
4.4 Administration
TRANEXAMIC ACID INJECTION is intended for intravenous injection or infusion only.
Erroneous administration of TRANEXAMIC ACID INJECTION via intrathecal and epidural routes has resulted in serious harm, including death (See WARNINGS AND PRECAUTIONS).
TRANEXAMIC ACID INJECTION is intended for intravenous administration (intravenous injection and infusion). TRANEXAMIC ACID INJECTION should be administered intravenously by slow injection over a period of at least 5 minutes. The recommended rate of bolus infusion is 50 mg/min. To administer 50 mg/min to the patient directly via intravenous injection, 0.5 mL/min of undiluted TRANEXAMIC ACID INJECTION (100 mg/mL) should be administered by slow intravenous injection. To administer 50 mg/min as an infusion, solutions diluted to 1% tranexamic acid (i.e. 1 g in 100 mL or 10 mg/mL), may be administered at 5 mL/min or solutions diluted to 2% tranexamic acid, may be administered at 2.5 mL/min.
5 OVERDOSAGE
There is no known case of overdosage of tranexamic acid in humans. Symptoms may include nausea, diarrhoea, dizziness, headache, convulsions, vomiting orthostatic symptoms and hypotension.
Treatment of overdosage would consist of initiating vomiting, institution of gastric lavage, charcoal therapy, and symptomatic treatment. Maintain adequate diuresis.
It has been seen that 37 g of tranexamic acid caused mild intoxication in a seventeen-year-old after gastric lavage.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 Dosage Forms, Strengths and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous | Solution / 100 mg/mL / tranexamic acid | Water for Injection |
Packaging
Tranexamic Acid Injection, 100 mg/mL ampoules are available in 500 mg / 5 mL and 1000 mg / 10 mL strengths, as a colorless solution, filled in single use clear glass ampoules with blue colour one point cut (OPC) marking. The ampoules are packed in cartons. The available pack size for 500 mg / 5 mL is 10 X 5 mL Ampoules and pack size for 1000 mg /10 mL is 10 X 10 mL Ampoules.
Tranexamic Acid Injection, 100 mg/mL, vials are available in 500 mg / 5 mL, 1000 mg / 10 mL and 5000 mg/ 50 mL strengths, as a colorless solution, filled in 5mL and 10mL USP type I glass clear vials, closed with siliconized rubber stopper (chlorobutyl grey) and sealed with aluminum with score lined plastic disc. The vials are packed in cartons. The available pack size for 500 mg / 5 mL is 10 X 5 mL vials and pack size, for 1000 mg /10 mL is 10 X 10 mL vials pack size and for 5000 mg/ 50 mL is 1 x 50 mL pharmacy bulk vials pack size.
Pharmacy Bulk vial
The use of pharmacy bulk vial is restricted to hospitals with recognized parenteral admixture program. The pharmacy bulk vial is intended for single puncture, multiple dispensing and for the preparation of admixtures only. Dispensing from a pharmacy bulk vial should be completed as soon as possible after initial entry.
7 WARNINGS AND PRECAUTIONS
General
The erroneous administration of tranexamic acid via intrathecal or epidural routes has been reported, resulting in serious adverse reactions including death.
Care should be exercised to confirm the correct route of administration, when other injectable medications are to be administered during the same procedure with TRANEXAMIC ACID INJECTION.
Cardiovascular
Venous and arterial thrombosis or thromboembolism has been reported in patients treated with tranexamic acid. Patients with a high risk for thrombosis (a previous thromboembolic event and a family history of thromboembolic disease) should use TRANEXAMIC ACID INJECTION only if there is a strong medical indication and under strict medical supervision.
Patients with disseminated intravascular coagulation (DIC), who require treatment with TRANEXAMIC ACID INJECTION, must be under the strict supervision of a physician experienced in treating this disorder.
Driving and Operating Machinery
Tranexamic acid may cause dizziness and therefore may influence the ability to drive or use machines.
Endocrine and Metabolism
Hormonal Contraceptives: Combination hormonal contraceptives are known to increase the risk of venous thromboembolism, as well as arterial thromboses such as stroke and myocardial infarction. Because TRANEXAMIC ACID INJECTION is an antifibrinolytic, concomitant use of hormonal contraception and TRANEXAMIC ACID INJECTION may further exacerbate this increased thrombotic risk. Women using hormonal contraception should use TRANEXAMIC ACID INJECTION only if there is a strong medical need and the benefit of treatment will outweigh the potential increased risk of a thrombotic event. The risk for thromboembolic events may be increased in patients using hormonal contraceptives. If TRANEXAMIC ACID INJECTION has to be used in these patients, advise them to use an effective alternative (nonhormonal) contraceptive method. (see 9 DRUG INTERACTIONS).
The following patients should consult their doctor prior to initiating treatment with TRANEXAMIC ACID INJECTION: obese and diabetic, with polycystic ovary syndrome or a history of endometrial cancer in a first-degree relative, women receiving unopposed oestrogen or tamoxifen.
Hematologic
Avoid concomitant use of TRANEXAMIC ACID INJECTION with medical products that are prothrombotic because concomitant use can further increase the risk of thromboembolic adverse reactions associated with tranexamic acid.
Patients with irregular menstrual bleeding should not use TRANEXAMIC ACID INJECTION until the cause of the irregularity has been established.
Patients should consult their doctor if menstrual bleeding is not reduced after three menstrual cycles.
If menstrual bleeding is not adequately reduced by TRANEXAMIC ACID INJECTION, an alternative treatment should be considered.
Patients taking anticoagulants (see 4.2 Recommended Dose and Dosage Adjustment).
Neurologic
Convulsions have been reported in association with tranexamic acid treatment.
Ophthalmologic
Visual disturbances including visual impairment, vision blurred, impaired color vision have been reported with tranexamic acid. For patients who are to be treated for several weeks with tranexamic acid, an ophthalmic check-up is advisable (sharpness of vision, colour vision, fundus, field of vision, etc.) if possible, before treatment is initiated and regularly during treatments.
Renal
Tranexamic acid therapy is not indicated in haematuria caused by diseases of the renal parenchyma. Intravascular precipitation of fibrin frequently occurs in these conditions and may aggravate the disease. In addition, in cases of massive renal hemorrhage of any cause, antifibrinolytic therapy carries the risk of clot retention in the renal pelvis.
Care should be taken in cases of renal insufficiency due to the risk of accumulation, and where there is pronounced haematuria from the upper urinary tract, since in isolated cases obstacles to passage have been observed in the tract (see 4.2 Recommended Dose and Dosage Adjustment).
Reproductive Health: Female and Male Potential
- Fertility
There are limited clinical data regarding the impact of tranexamic acid on fertility.
Tranexamic acid passes into the semen and inhibits its fibrinolytic activity, but without affecting the motility of the spermatozoa.
Sensitivity/Resistance
Cases of allergic reaction with use of intravenous tranexamic acid, including anaphylaxis or anaphylactoid reaction have been reported that are suggestive of a causal relationship. Patients should be closely monitored for the possibility of a severe allergic reaction occurring following its administration.
7.1 Special Populations
7.1.1 Pregnant Women
Tranexamic acid passes through the placenta. The concentration in cord blood after an intravenous injection of 10 mg/kg to pregnant women is about 30 mg/L, as high as in the maternal blood.
Fibrinolytic activity is very high in neonates. It is not known for certain whether a reduction of this activity during the first hours of life is harmful. Kullander and Nilsson who have wide experience with tranexamic acid in connection with childbirth have observed no negative effect on the infants.
For decisions regarding the use of tranexamic acid during pregnancy, the potential risk of tranexamic acid administration on the fetus should always be considered along with the mother’s clinical need for tranexamic acid; an accurate risk-benefit evaluation should drive the treating physician’s decision.
Available data from published studies, case series and case reports with tranexamic acid use in pregnant women in the second and third trimester and at the time of delivery have not clarified whether there is a drug-associated risk of miscarriage or adverse maternal or fetal outcomes. There are cases of fetal structural abnormalities that resulted in death of the newborn following administration of tranexamic acid to the mother during conception or the first trimester of pregnancy; however, due to other confounding factors the actual risk of major birth defects with use of tranexamic acid during pregnancy is not clear.
There were 13 clinical studies that described fetal and/or neonatal functional issues such as low Apgar score, neonatal sepsis, cephalohematoma and 9 clinical studies that discussed alterations to growth including low birth weight and preterm birth at 22-36 weeks of gestation in fetuses and infants exposed to tranexamic acid in utero.
A woman with fibrinolytic bleeding in the fourth month of pregnancy was treated with tranexamic acid for a total of 64 days. The total dose was 256 g. The delivery occurred spontaneously in the 30th week of pregnancy and was normal in all other respects. The infant was healthy.
In a case of threatened placental abruption that was prevented by giving tranexamic acid, the patient had already lost two children in connection with placental abruption. In the 26th week of her third pregnancy bleeding occurred, indicating abruption. Pathological proteolysis with predominant activation of the fibrinolytic system was established. Between the 26th and 33rd week of pregnancy about 250 g of tranexamic acid were given, both intravenously and orally. The bleeding was arrested, and a healthy child was delivered by Caesarean section.
The estimated background risk for major birth defects and miscarriage for the indicated human population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
7.1.2 Breast-feeding
Tranexamic acid is secreted in the mother’s milk at a concentration of only a hundredth of the corresponding serum levels.
Published literature reports the presence of tranexamic acid in human milk. There are no data on the effects of tranexamic acid on the breastfed child or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for tranexamic acid and any potential adverse effects on the breastfed child from tranexamic acid or from the underlying maternal condition.
7.1.3 Pediatrics
No data are available to Health Canada for TRANEXAMIC ACID INJECTION for intravenous administration; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Clinical studies of tranexamic acid did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. See 1.2 Geriatrics.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Gastrointestinal Disorders: Gastrointestinal symptoms (nausea, vomiting, diarrhea) occur but disappear when the dose is reduced.
Immune System Disorders: allergic dermatitis has been reported less commonly.
Nervous System Disorders: Isolated cases of dizziness or reduced blood pressure have been reported
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Eye Disorders: No retinal changes have been reported or observed at ophthalmic check-ups of patients treated with tranexamic acid for several weeks or months. This is despite experimental findings in animals (dog and cat) where retina changes have been observed after long-term administration of large doses of tranexamic acid.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Additional data is not available for the pediatric population that is any different from the adult population (see section 8.1).
8.3 Less Common Clinical Trial Adverse Reactions
See section 8.1.
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
Additional data is not available for the pediatric population that is any different from the adult population (see section 8.1).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
No data is available regarding abnormal laboratory findings and tranexamic acid therapy.
8.5 Post-Market Adverse Reactions
Rare cases of adverse events have been reported with the use of tranexamic acid.
Eye Disorders: impaired vision, blurred vision or colour vision impairment (chromatopsia)
Immune System Disorders: Cases of allergic reaction with use of intravenous tranexamic acid, including anaphylaxis or anaphylactoid reaction have been reported that are suggestive of a causal relationship.
Nervous System Disorders: dizziness and seizures
Vascular Disorders: thromboembolic events (acute myocardial infarction, thrombosis, arterial thrombosis limb, carotid artery thrombosis, cerebral infarction, cerebrovascular accident, deep vein thrombosis, pulmonary embolism, cerebral thrombosis, acute renal cortical necrosis, and central retinal artery and vein obstruction). Hypotension may occur after fast injection.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No studies of interactions between tranexamic acid and other drugs have been conducted. Because of the absence of interaction studies, simultaneous treatment with anticoagulants must take place under the strict supervision of a physician experienced in this field.
9.4 Drug-Drug Interactions
Because tranexamic acid is an antifibrinolytic, avoid concomitant use of TRANEXAMIC ACID INJECTION with medical products that are prothrombotic because concomitant use can further increase the risk of thromboembolic adverse reactions associated with tranexamic acid.
Potential drug-drug interactions may lead to myocardial infarction after coadministration with hormonal contraceptives, hydrochlorothiazide, desmopressin, sulbactam-ampicillin, carbazochrome, ranitidine, or nitroglycerin. Concomitant use of hormonal contraception and TRANEXAMIC ACID INJECTION may further exacerbate the increased thrombotic risk associated with combination hormonal contraceptives (see 7 WARNINGS AND PRECAUTIONS).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Tranexamic acid produces an antifibrinolytic effect by competitively inhibiting the activation of plasminogen to plasmin. It is also a weak non-competitive inhibitor of plasmin. These properties make possible its clinical use as an antifibrinolytic in the treatment of both general and local fibrinolytic hemorrhages. It has an action mechanism similar to, but about 10 times more potent in vitro, than that of E amino caproic acid (EACA).
Tranexamic acid binds considerably more strongly than EACA to both the strong and weak sites in the plasminogen molecule in a ratio corresponding to the difference in potency between the compounds. The pharmacological significance of the binding to these different sites has not yet been evaluated.
The therapeutic plasma concentration of tranexamic acid is 5-15 mg/L. The functional interaction between plasminogen and tissue activator, located mainly on fibrin, is prevented by dissociation of the complex between fibrin and specific substrate binding sites on plasminogen. A potentiating effect on natural inhibitors also appears to contribute to the clinical effect during antifibrinolytic therapy.
10.2 Pharmacodynamics
When administered 36-48 hours before surgery in four doses of 10-20 mg per kg body weight, an antifibrinolytically active concentration (10 mcg/mL) of tranexamic acid remained up to 17 hours in the tissues investigated, and up to 7-8 hours in the serum.
Tranexamic acid (5 x 10⁻²M) competitively inhibits the activation of trypsinogen by enterokinase and non-competitively inhibits the proteolytic activity of trypsin at 4-fold greater concentration. While aminocaproic acid moderately inhibits trypsin (40%), urinary kallikrein (30%) and pancreatic kallikrein (60%), Tranexamic acid has little effect (less than 10%) on any of these enzymes.
A still weaker effect is exerted on thrombin (7 x 10⁻³M, 100 mg/L). Tranexamic acid (7 x 10⁻²M) added to blood has no influence on the platelet count, coagulation time, one-stage prothrombin time or recalcification time. The plasma levels of AHF, Factor IX, prothrombin, Factor VII, Factor V and fibrinogen also remain unchanged in vitro.
Tranexamic acid (7 x 10⁻³M, 1 g/L) does not aggregate human platelets in vitro. On the contrary in vivo (dogs) a dose of 30 mg/kg I.V. showed a decreased ADP-induced aggregability and a stabilizing effect on glass bead adhesiveness for 24 hours after the administration.
The activity of chymotrypsin is not impaired by synthetic antifibrinolytics and an inhibition of the action of pepsin is observed only in high concentrations, 6 x 10⁻³M. The degradation of bradykinin in human plasma is not significantly inhibited at 10-2M.
Tranexamic acid administered by I.V. infusion in the anaesthetized cat in doses of 0.4-2 mg/kg/min for 60 minutes and i.m. in the rabbit, cat and dog in doses of 170 mg/kg do not cause significant changes in arterial blood pressure, respiration of ECG.
The mechanism of the cardiovascular effect of Tranexamic acid is less clear than that of E-amino caproic acid, which appears to produce an indirect sympathomimetic effect. In relation to its therapeutic effect Tranexamic acid has about 10 times less potent effect than EACA on blood pressure. Threshold doses to produce increase in the blood pressure and heart rate are 50-100 mg/kg for Tranexamic acid and 30-50 mg/kg for EACA in anaesthetized cats, corresponding to a human equivalent dose of 160-320 mg/kg for tranexamic acid and 96-160 mg/kg for EACA.
10.3 Pharmacokinetics
Absorption
Absorption from the human gastrointestinal tract is not complete (40%).
Three hours after a single oral dose of 25 mg per kg body weight, the peak serum level was 15.4 mg per L and the aqueous humour level was 1.6 mg per L.
Distribution
Tranexamic acid does not bind to serum albumin. The plasma protein binding seems to be fully accounted for by its binding to plasminogen and appears to be negligible at therapeutic plasma levels of 5-10 mg/L.
Intravenous administration of 10 mg per kg body weight gave plasma concentrations of 18.3 mcg, 9.6 mcg and 5 mcg per mL one, three and five hours after the injection.
The ability of tranexamic acid to cross the blood brain barrier has been demonstrated when administered to patients with ruptured intracranial aneurysms.
Tranexamic acid diffuses rapidly to the joint fluid and to the synovial membrane. In the joint fluid the same concentration was obtained as in the serum. The biological half-life in the joint fluid was about 3 hours.
Metabolism
Possible routes of biotransformation are acetylation or deamination followed by oxidation or reduction.
Elimination
Tranexamic acid is eliminated by glomerular filtration, excretion being about 30% at one hour, 55% at three hours and 90% at 24 hours after intravenous administration of 10 mg per kg body weight.
Special Populations and Conditions
Pediatrics
Clinical experience with tranexamic acid in menorrhagic children under 18 years of age is not available.
Pregnancy and Breast-feeding
Tranexamic acid crosses the placenta. After an intravenous injection of 10 mg per kg the concentration can rise to about 30 mcg per mL of fetal serum.
Tranexamic acid also passes over into the breast milk during lactation in concentrations 1/100 of the corresponding serum levels.
Renal Insufficiency
See 4.2 Recommended Dose and Dosage Adjustment.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15 - 30°C).
Once the product is reconstituted, the mixture should be used immediately after preparation. If storage is necessary, the mixture should be stored at 2 – 8oC for a maximum of 24 hours. Mixture not used within 24 hours of preparation, should be discarded.
The ampoules and vials of TRANEXAMIC ACID INJECTION are sterile. TRANEXAMIC ACID INJECTION is intended for single use. Unused product must be discarded. As with all parenteral drug products, TRANEXAMIC ACID INJECTION should be inspected visually for clarity, particulate matter, precipitation, discolouration and leakage prior to administration, whenever solution and container permit.
Keep your medicine out of the reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
None
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Tranexamic acid
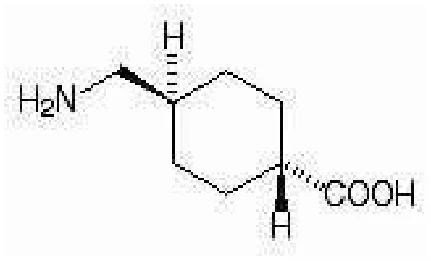
Chemical Name: trans-4 (Aminomethyl) cyclohexanecarboxylic acid
Molecular Formula and Molecular Weight: C8H15NO2 and 157.21 g/mol
Structural Formula:
Physicochemical properties
White, or almost white crystalline powder.
Freely soluble in water and in glacial acetic acid, practically insoluble in acetone and in alcohol.
6.5 to 8.0
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
- The data is not available.
14.2 Comparative Bioavailability Studies
- The data is not available.
14.3 Immunogenicity
- The data is not available.
14.4 Clinical Trials – Reference Biologic Drug
- The data is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Nonclinical studies have shown a retinal toxicity associated with tranexamic acid. Toxicity is characterized by retinal atrophy commencing with changes to the retinal pigmented epithelium and progressing to retinal detachment in cats. The toxicity appears to be dose related, and changes are partially reversible at lower doses. Effects (some fully reversible) are seen in cats at clinically relevant doses. In the dog, effects were only observed at extremely high dose levels of 2 x 400 mg/kg/day and peak plasma levels of about 200 mg per litre. By comparison, in humans peak plasma levels are in the range of 10-20 mg per litre after a therapeutic oral dose of about 30 mg/kg body weight.
Studies suggest that the underlying mechanism for retinal toxicity may be related to a transient retinal ischemia at higher dose exposures, linked to the known sympathomimetic effect of high plasma levels of tranexamic acid. The clinical relevance of these findings is unknown.
In subacute toxicity studies, daily doses of Tranexamic acid administered orally to rats (1 to 5 g/kg for 10 weeks) and dogs (100 to 500 mg/kg for 4 months) and intraperitoneally to rats (0 to 1000 mg/kg for 2 weeks) resulted in dose-related emesis, loose stools or diarrhea, and decreased body weight gain.
Intravenous administration of tranexamic acid to rabbits (60 to 180 mg/kg for 13 days) resulted in dose-related tachypnea.
In the 1-month intravenous study in dogs given 20, 100 or 500 mg/kg/day emesis and salivation occurred at the two highest dose levels. Microscopically, pulmonary thromboembolism was found in one dog receiving the intermediate dose and one from the high dose group. The latter dog also had two thrombophletitides in the urinary bladder. No cardiac hemorrhages were found.
Epileptogenic activity has been observed in animals with intrathecal use of tranexamic acid. No other significant observations have been made in general toxicology studies.
Carcinogenicity
In one of the carcinogenicity studies in which rats were given tranexamic acid in high doses, biliary hyperplasia, cholangioma and adenocarcinoma of the liver were found.
These findings have not been reproduced in a number of subsequent carcinogenicity studies. An increased incidence of leukemia (although not statistically significant) occurred in one study in mice given 4.8 percent Tranexamic acid for 20 months. In other studies, the frequency and histologic appearance of the observed tumors were similar in the test groups and in the untreated animals.
Reproductive and Development Toxicology:
In reproductive toxicity studies, tranexamic acid had no adverse effect on reproductive parameters of mice, rats and rabbits at clinically relevant doses.
17 SUPPORTING PRODUCT MONOGRAPHS
1 PrCYKLOKAPRON® (Solution, 100 mg/mL, Intravenous), Submission Control Number: 254356, Product Monograph, Pfizer Canada ULC. NOV 25, 2021