


Product Monograph - Vyvgart
Recent Major Label Changes
| 7 Warnings and Precautions, Immune | 2025-07 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
1 Indications .................................................................................................................. 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 Contraindications ........................................................................................................ 4
4 Dosage and Administration ......................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment ..................................................... 4
4.3 Reconstitution ...................................................................................................... 5
4.4 Administration ...................................................................................................... 5
4.5 Missed Dose ......................................................................................................... 6
5 Overdose..................................................................................................................... 6
6 Dosage Forms, Strengths, Composition, and Packaging ............................................... 6
7 Warnings and Precautions ........................................................................................... 7
Immune ............................................................................................................................ 7
Reproductive Health ........................................................................................................ 7
Sensitivity/Resistance ....................................................................................................... 7
7.1 Special Populations ............................................................................................... 8
7.1.1 Pregnancy ......................................................................................................... 8
7.1.2 Breastfeeding ................................................................................................... 8
7.1.3 Pediatrics .......................................................................................................... 8
7.1.4 Geriatrics .......................................................................................................... 8
8 Adverse Reactions ....................................................................................................... 8
8.1 Adverse Reaction Overview .................................................................................. 8
8.2 Clinical Trial Adverse Reactions ............................................................................ 9
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 10
9 Drug Interactions ...................................................................................................... 10
9.2 Drug Interactions Overview ................................................................................ 10
9.3 Drug-Behaviour Interactions .............................................................................. 10
9.4 Drug-Drug Interactions ....................................................................................... 10
9.5 Drug-Food Interactions ....................................................................................... 10
9.6 Drug-Herb Interactions ....................................................................................... 10
9.7 Drug-Laboratory Test Interactions ...................................................................... 10
10 Clinical Pharmacology ............................................................................................... 11
10.1 Mechanism of Action .......................................................................................... 11
10.2 Pharmacodynamics ............................................................................................ 11
10.3 Pharmacokinetics ............................................................................................... 11
10.4 Immunogenicity .................................................................................................. 12
11 Storage, Stability, and Disposal ................................................................................. 12
Part 2: Scientific Information ................................................................................................ 13
13 Pharmaceutical Information ...................................................................................... 13
14 Clinical Trials ............................................................................................................. 14
14.1 Clinical Trials by Indication ................................................................................. 14
16 Non-Clinical Toxicology ............................................................................................. 16
Patient Medication Information ........................................................................................... 18
Part 1: Healthcare Professional Information
1 Indications
VYVGART® (efgartigimod alfa for injection) is indicated for the treatment of adult patients with generalized myasthenia gravis (gMG) who are anti-acetylcholine receptor (AChR) antibody positive.
1.1 Pediatrics
Pediatrics (˂ 18 years of age): The safety and efficacy of VYVGART in children and adolescents below the age of 18 years has not been established. VYVGART is not indicated for use in pediatric patients.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Eleven (11/84 – 13%) patients aged 65 and over were treated with VYVGART in the placebo-controlled study. The number of patients aged 65 and over is not sufficient to determine whether they respond differently from younger adult patients.
2 Contraindications
VYVGART is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4 Dosage and Administration
4.2 Recommended Dose and Dosage Adjustment
Dilute VYVGART prior to administration. Administer via intravenous infusion only. See 4.3 Reconstitution.
The recommended dosage of VYVGART is 10 mg/kg administered as an intravenous infusion over one hour once weekly for 4 weeks (one treatment cycle). In patients weighing 120 kg or more, the recommended dose of VYVGART is 1200 mg (3 vials) per infusion.
Administer subsequent treatment cycles based on clinical evaluation. The frequency of VYVGART treatment cycles may vary by patient. The safety of initiating subsequent cycles sooner than 4 weeks from the last infusion of the previous treatment cycle has not been established.
Pediatrics (˂ 18 years of age): The safety and efficacy of VYVGART in children and adolescents below the age of 18 years has not been established. VYVGART is not indicated for use in pediatric patients.
Geriatrics (≥ 65 years of age): Eleven (11/84 – 13%) patients aged 65 and over were treated with VYVGART in the placebo-controlled study. The number of patients aged 65 and over is not sufficient to determine whether they respond differently from younger adult patients.
Renal Impairment: No dose adjustment of VYVGART is needed for patients with mild renal impairment. There is very limited safety and efficacy data in patients with moderate renal impairment (eGFR 30-59mL/min/1.73 m2) and no safety and efficacy data in patients with severe renal impairment (eGFR <30 mL/min/1.73 m2). (see 10 Clinical Pharmacology)
4.3 Reconstitution
Parenteral Products:
Prior to administration, VYVGART single-use vials require dilution in 0.9% Sodium Chloride Injection, USP, to make a total volume to be administered of 125 mL.
Check that the VYVGART solution is clear to slightly opalescent and colorless to slightly yellow. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Do not use if opaque particles, discoloration, or other foreign particles are present. Use aseptic technique when preparing the VYVGART diluted solution for intravenous infusion. Each vial is for single-use only.
Discard any unused portion in accordance with local requirements.
Preparation
- Calculate the dose (mg), total drug volume (mL) of VYVGART solution required, and the number of vials needed based on the recommended dose according to the patient's body weight. Each vial contains a total of 400 mg of VYVGART at a concentration of 20 mg per mL. See 4.2 Recommended Dose and Dosage Adjustment.
- Gently withdraw the calculated dose of VYVGART from the vial(s) with a sterile syringe and needle. Discard any unused portion of the vials in accordance with local requirements.
- Dilute the withdrawn VYVGART with 0.9% Sodium Chloride Injection, USP to make a total volume of 125 mL for intravenous infusion.
- Gently invert the infusion bag containing the diluted VYVGART without shaking to ensure thorough mixing of the product and the diluent.
- The diluted solution can be administered using polyethylene (PE), polyvinyl chloride (PVC), ethylene vinyl acetate (EVA), or ethylene/polypropylene copolymer bags (polyolefins bags), and with PE, PVC, EVA, or polyurethane/polypropylene infusion lines.
Storage Conditions of the Diluted Solution
- VYVGART does not contain preservatives. Administer immediately after dilution and complete the infusion within 4 hours of dilution.
- If immediate use is not possible, the diluted solution may be stored refrigerated at 2°C to 8°C (36°F to 46°F) for up to 8 hours. Do not freeze. Protect from light. Allow the diluted drug to reach room temperature before administration. Complete the infusion within 4 hours of removal from the refrigerator. Do not heat the diluted drug in any manner other than via ambient air. See 11 Storage, Stability, and Disposal.
4.4 Administration
- VYVGART should be administered via intravenous infusion by a healthcare professional.
- Visually inspect VYVGART diluted solution for particles or discoloration prior to administration. Do not use if discolored, or if opaque or foreign particles are seen.
- Infuse the total 125 mL of diluted solution intravenously over one hour via a 0.2 micron in-line filter.
- After administration of VYVGART, flush the entire line with 0.9% Sodium Chloride Injection, USP.
Monitor patients during administration and for 1 hour thereafter for clinical signs and
- symptoms of infusion reactions. Should a reaction occur, discontinue the infusion and institute appropriate supportive measures, if needed. Once resolved, and based on the severity of the reaction, administration may be cautiously resumed, if needed at a slower rate based on clinical evaluation. See 7 Warnings and Precautions, Sensitivity/Resistance.
- Other medications should not be injected into infusion side ports or mixed with VYVGART.
4.5 Missed Dose
If a scheduled infusion is missed, VYVGART may be administered up to 3 days after the scheduled time point. Thereafter, resume the original dosing schedule until the treatment cycle is completed.
5 Overdose
There are no known specific signs and symptoms of overdose with VYVGART. In the event of an overdose the adverse events are not expected to be different from those observed at the recommended dose. Patients should be monitored for adverse reactions and appropriate symptomatic and supportive treatment initiated. There is no specific antidote for overdose with VYVGART.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Two intravenous formulations are marketed. The only difference between the formulations (“Formulation 1” and “Formulation 2”) is the excipient composition (see Table 1). There are no changes to the active ingredient, strength, dosage form, route of administration or clinical use.
Table 1: Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients | |
| Formulation 1 | Intravenous | 20 mg/mL efgartigimod alfa solution | L-arginine hydrochloride, polysorbate 80, sodium chloride, sodium phosphate dibasic anhydrous, sodium phosphate monobasic monohydrate, water for injection |
| Formulation 2 | Intravenous | 20 mg/mL efgartigimod alfa solution | L-arginine hydrochloride, L-histidine, L-histidine hydrochloride monohydrate, L-methionine, polysorbate 80, sodium chloride, sucrose, water for injection |
Description
VYVGART (efgartigimod alfa for injection) is a preservative free, sterile, colorless to slightly yellow, clear to slightly opalescent solution supplied as 400 mg/20 mL (20 mg/mL) in one single-use vial.
7 Warnings and Precautions
Immune
Infections
As VYVGART causes a reduction in IgG levels, the risk of infections may increase. The most common infections observed in clinical trials were upper respiratory tract infections and urinary tract infections. While the majority of infections were mild to moderate in severity, serious infections were reported. See 8.2 Clinical Trial Adverse Reactions. Monitor for clinical signs and symptoms of infections during treatment with VYVGART. Delay VYVGART administration in patients with an active infection until the infection is resolved. If a serious infection occurs, administer appropriate treatment and consider withholding VYVGART until the infection has resolved.
Immunization
Administer all vaccines according to immunization guidelines at least 4 weeks before initiation of treatment with VYVGART.
The safety of immunization with live vaccines and the immune response to vaccination during treatment with VYVGART are unknown. Because VYVGART causes a reduction in IgG levels, vaccination with live vaccines is not recommended during treatment with VYVGART.
For all other vaccines, vaccination should take place at least 2 weeks after the last infusion of a treatment cycle and 4 weeks before initiating the next cycle.
Reproductive Health
Fertility
There is no clinical experience with VYVGART use and its potential effect on fertility.
Sensitivity/Resistance
Hypersensitivity and Infusion related reactions
Hypersensitivity reactions such as rash, pruritus or anaphylactic reactions may occur. In clinical trials, infusion-related reactions were mild or moderate and did not lead to treatment discontinuation. Monitor patients during administration and for 1 hour thereafter for clinical signs and symptoms of infusion reactions. Should a reaction occur, discontinue the infusion and institute appropriate supportive measures, if needed. Once resolved, and based on the severity of the reaction, administration may be cautiously resumed, if needed at a slower rate based on clinical evaluation (See 4.4 Administration).
Patients should be informed of the signs and symptoms of hypersensitivity reactions and advised to contact their healthcare provider immediately should they occur.
7.1 Special Populations
7.1.1 Pregnancy
There are no available clinical data on the use of VYVGART during pregnancy. Reproductive and developmental toxicity studies were conducted in rats and rabbits. See 16 Non-clinical toxicology.
Monoclonal antibodies are increasingly transported across the placenta as pregnancy progresses, with the largest amount transferred during the third trimester. Therefore, VYVGART may be transmitted from the mother to the developing fetus. As VYVGART is expected to reduce maternal IgG antibody levels, and is also expected to inhibit the transfer of maternal antibodies to the fetus, reduction in passive protection to the newborn is anticipated. Risk and benefits should be considered prior to administering live or live-attenuated vaccines to infants exposed to VYVGART in utero.
7.1.2 Breastfeeding
There is no information regarding the presence of VYVGART in human milk, the effects on the breastfed infant, or the effects on milk production. Maternal IgG is known to be present in human milk. A risk to the breastfed newborn/infant cannot be excluded.
The developmental and health benefits of breastfeeding and the mother's clinical need for VYVGART should be considered, as well as any potential adverse effects on the breastfed infant from VYVGART or from the underlying maternal condition.
7.1.3 Pediatrics
Pediatrics (˂18 years): The safety and efficacy of VYVGART in children and adolescents below the age of 18 years has not been established. VYVGART is not indicated for use in pediatric patients.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Eleven (11/84 – 13%) patients aged 65 and over were treated with VYVGART in the placebo-controlled study. The number of patients aged 65 and over is not sufficient to determine whether they respond differently from younger adult patients.
8 Adverse Reactions
8.1 Adverse Reaction Overview
In the placebo-controlled Phase 3 Study ARGX-113-1704 (Study 1704), the most common adverse reactions (≥ 10%) seen in patients who received at least one dose of VYVGART included headache (reported by 29% of VYVGART-treated patients and 28% of placebo-treated patients), upper respiratory tract infection (reported by 11% of VYVGART-treated patients and 5% of placebo-treated patients), and urinary tract infection (reported by 10% of VYVGART-treated patients and 5% of placebo-treated patients) (Table 2). Adverse reactions of severity Grade ≥3 (according to the Common Terminology Criteria for Adverse Events) were reported by 11% (9/84) of VYVGART-treated patients and 10% (8/83) of placebo-treated patients. The proportion of patients treated with VYVGART who discontinued treatment due to adverse reactions was 4% (3/84).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to the frequencies reported in clinical trials of another drug.
In the placebo-controlled Phase 3 study (Study 1704) in patients with gMG, 84 patients received VYVGART 10 mg/kg. See 14 Clinical Trials. The frequency of VYVGART treatment cycles at the recommended dose regimen varied by patient. See 4 Dosage and Administration. The safety of initiating subsequent cycles sooner than 4 weeks from the last infusion of the previous treatment cycle has not been established.
A total of 21/84 (25%) patients on VYVGART received a single treatment cycle, 56/84 (67%) patients received 2 treatment cycles, and 7/84 (8%) patients received 3 treatment cycles. The mean and median times to the second treatment cycle were 94 days and 72 days from the initial infusion of the first treatment cycle, respectively.
Adverse reactions reported in at least 5% of patients treated with VYVGART and more frequently than placebo (≥ 3 patients) are summarized Table 2.
Table 2: Adverse Reactions Reported in ≥ 5% of Patients with Myasthenia Gravis Treated With VYVGART and More Frequently Than in Placebo-Treated Patients (≥ 3 patients) in Study ARGX-113-1704
| Adverse Reaction | VYVGART (N=84) n (%) | Placebo (N=83) n (%) | ||
|---|---|---|---|---|
| Infections and Infestations | ||||
| Bronchitis | 5 (6) | 2 (2) | ||
| Upper Respiratory Tract Infection | 9 (11) | 4 (5) | ||
| Urinary Tract Infection | 8 (10) | 4 (5) | ||
| Injury, poisoning and Procedural Complications | ||||
| Procedural Headache | 4 (5) | 1 (1) | ||
| Musculoskeletal and Connective Tissue Disorders | ||||
| Myalgia | 5 (6) | 1 (1) | ||
Infections
The most frequently reported adverse reactions were infections. Overall, treatment emergent infections were reported in 46% (n=39) of patients treated with VYVGART and 37% (n=31) of patients treated with placebo. The most reported infections were upper respiratory tract infections and urinary tract infections. A higher frequency of patients who received VYVGART compared to placebo were observed to have below normal levels for white blood cell counts (12% versus 5%, respectively), lymphocyte counts (28% versus 19%, respectively), and neutrophil counts (13% versus 6%, respectively). The majority of infections and hematology abnormalities were mild to moderate in severity. Serious infections have been reported in patients treated with VYVGART.
Procedural headache
Procedural headache was reported in 4.8% of the patients treated with VYVGART and 1.2% of patients treated with placebo. Procedural headache was reported when a headache was judged to be temporally related to the intravenous infusion of VYVGART. All were mild or moderate except one event which was reported as severe (Grade 3).
8.3 Less Common Clinical Trial Adverse Reactions
Clinical trial adverse reactions occurring in ˂5% of Patients with Myasthenia Gravis treated with VYVGART and more frequently than in placebo-treated patients (≥ 2 patients) in Study ARGX-113-1704 are as follows:
Eye Disorders: visual impairment
General Disorders and Administration Site Conditions: pain
Immune System Disorders: seasonal allergy
Infections and Infestations: ear infection, sinusitis
Injury, Poisoning and Procedural Complications: skin abrasion
Nervous System Disorders: migraine, hypoesthesia
9 Drug Interactions
9.2 Drug Interactions Overview
Clinical drug interactions studies have not been performed with VYVGART.
9.3 Drug-Behaviour Interactions
The interaction of VYVGART with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
VYVGART may decrease concentrations of compounds that bind to the human FcRn, such as, immunoglobulin products, monoclonal antibodies, or antibody derivates containing the human Fc domain of the IgG subclass. Patients receiving VYVGART while concomitantly on treatment with these products should be closely monitored for the altered efficacy response to these products. If possible, it is recommended to postpone initiation of treatment with these products to two weeks after the last dose of any given treatment cycle of VYVGART.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Efgartigimod alfa is a human IgG1 antibody fragment that binds to neonatal Fc receptor (FcRn) and inhibits its interaction with IgG. This results in increased degradation of IgG and reduction of circulating IgG and pathological IgG autoantibodies.
10.2 Pharmacodynamics
In the placebo-controlled study in gMG patients (see 14 Clinical Trials), the pharmacological effect of efgartigimod alfa was assessed by measuring the decrease in serum IgG levels and AChR autoantibody levels. In patients who were tested positive for AChR antibodies and treated with efgartigimod alfa at the recommended dose and schedule (see 4 Dosage and Administration), the mean percentage decrease in total IgG levels compared to baseline reached 61% one week after the last infusion of the initial treatment cycle and returned to baseline levels 9 weeks after the last infusion. Decrease in AChR autoantibody levels followed a similar time course.
10.3 Pharmacokinetics
Efgartigimod alfa exhibits linear pharmacokinetics, and following single doses of efgartigimod alfa, exposures increase proportionally up to 50 mg/kg (5 times the recommended dosage).
Distribution
The volume of distribution is 15 to 20L.
Metabolism
Efgartigimod alfa is expected to be degraded by proteolytic enzymes into small peptides and amino acids.
Elimination
After a single intravenous dose of 10 mg/kg efgartigimod alfa in healthy subjects, less than 0.1% of the administered dose was recovered in urine.
The terminal half-life is 80 to 120 hours (3 to 5 days).
Special populations and conditions
- Age, gender, and race: A population pharmacokinetics analysis assessing the effect of age, gender, and race did not suggest clinically significant impact of these covariates on efgartigimod alfa exposures.
- Hepatic Insufficiency: No dedicated pharmacokinetic study has been performed in patients with hepatic impairment. Hepatic impairment is not expected to affect the pharmacokinetics of efgartigimod alfa.
- Renal Insufficiency: No dedicated pharmacokinetic study has been performed in patients with renal impairment. Based on a population PK analysis of data from the VYVGART clinical studies, patients with mild renal impairment (eGFR 60-89 mL/min/1.73m²) had 22% increase in exposure relative to the exposure in patients with normal renal function. The impact of moderate renal impairment (eGFR < 60 mL/min/1.73m²) on VYVGART exposure could not be assessed since the number of patients was too small (N = 3).
10.4 Immunogenicity
As with all therapeutic proteins, there is a potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay.
In Study 1704, antibodies to VYVGART were detected in 17/83 (21%) patients. Neutralizing antibodies were detected in 6/83 (7%) patients treated with VYVGART. Data was not sufficient to conclude whether there is clinically meaningful impact of antibodies to VYVGART on the efficacy, safety, pharmacokinetics and pharmacodynamic of VYVGART.
11 Storage, Stability, and Disposal
VYVGART (efgartigimod alfa for injection) is a preservative free, sterile, colorless to slightly yellow, clear to slightly opalescent solution supplied as 400 mg/20 mL (20 mg/mL) in one single-use vial.
Store VYVGART vials refrigerated at 2°C to 8°C in the original carton to protect from light until time of use. Do not freeze. Do not shake.
See 4.3 Reconstitution for information on stability and storage of the diluted solutions of VYVGART.
Discard the vial containing unused portion of VYVGART in accordance with local requirements.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: efgartigimod alfa
Chemical name: efgartigimod; human recombinant immunoglobulin G1 AbdegTM Fc fragment
Molecular formula and molecular mass: The theoretical mass for efgartigimod is 53,915 Da based on the lysine clipped amino acid sequence with 2 x G0F glycans at 100% occupancy, and has been confirmed by peptide mapping experiments.
Structural formula: The efgartigimod Fc fragment is a homodimer consisting of two identical peptide chains each consisting of 227 amino acids. The peptide chains are linked together by two interchain disulfide bonds at positions Cys226 and Cys229. Every peptide chain includes two intrachain disulfide bonds at positions Cys261-Cys321 and Cys367-Cys425. Efgartigimod contains an N-glycosylation site at position Asn297 with the predominant glycan being of the G0F format. The C-terminal lysine is predominantly clipped.
Physicochemical properties: Efgartigimod is a clear to slightly opalescent, colorless to slightly yellow solution that has an extinction coefficient (280 nm) that is theoretically 1.33 mg/mL-1cm-1 and was experimentally seen as 1.44 mg/mL-1cm-1. The pI (isoelectric point) of the main isoform is approximately 7.2.
Product Characteristics: Efgartigimod alfa is a human immunoglobulin G1 (IgG1)-derived Fc fragment engineered to have increased affinity for the neonatal Fc receptor (FcRn). Efgartigimod alfa is produced in Chinese hamster ovary (CHO) cells by recombinant DNA technology.
14 Clinical Trials
14.1 Clinical Trials by Indication
- Generalized Myasthenia Gravis
Trial Design and Study Demographics
Table 3: Summary of Patient Demographics for Clinical Trials in Myasthenia Gravis
| Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
| ARGX-113-1704 | Phase 3 randomized double-blinded placebo-controlled | EFG IV solution Cycles of 10 mg/kg EFG or PBO every week x 3 weeks (4 infusions total) for up to 28 weeks | 167 patients randomized AChR-Ab seropositive: 129 AChR-Ab seronegative: 38 EFG arm: 84 PBO arm: 83 | EFG arm: 45.9 years (19 – 78 years) PBO arm: 48.2 years (19 – 81 years) | EFG arm: 63 females / 21 males PBO arm: 55 females / 28 males |
EFG = efgartigimod alfa; IV = intravenous; PBO = placebo; AChR-Ab = acetylcholine receptor antibody
The efficacy of VYVGART for the treatment of generalized myasthenia gravis (gMG) in adults was established in a 26-week, multicenter, randomized, double-blind, placebo-controlled trial.
Study 1704 enrolled patients who met the following criteria at screening:
- Myasthenia Gravis Foundation of America (MGFA) clinical classification class II to IV
- Myasthenia Gravis Activities of Daily Living (MG-ADL) total score of ≥ 5
- On stable dose of MG therapy prior to screening, that included acetylcholinesterase (AChE) inhibitors, steroids, or non-steroidal immunosuppressive therapies (NSISTs), either in combination or alone
- IgG levels of at least 6 g/L
A total of 167 patients were enrolled in Study 1704 and were randomized to receive either VYVGART 10 mg/kg (1200 mg for those weighing 120 kg or more) (n=84) or placebo (n=83). Baseline characteristics were similar between treatment groups. Patients had a median age of 46 years at screening (range: 19 to 81 years) and a median time since diagnosis of 9 years. Seventy-one percent were female, and 84% were White. Median MG-ADL total score was 9, and median Quantitative Myasthenia Gravis (QMG) total score was 16. The majority of patients (77% in each group) tested positive for antibodies to AChR (AChR-Ab). Of the 38 (23%) patients that tested negative for AChR-Ab, 3 patients in each treatment group tested positive for MuSK autoantibodies.
During the study, over 80% of patients in each group received AChE inhibitors, over 70% in each treatment group received steroids, and approximately 60% in each treatment group received NSISTs, at stable doses. At study entry, approximately 30% of patients in each treatment group had no previous exposure to NSISTs.
Patients were treated with VYVGART at the recommended dosage regimen and received a maximum of 3 treatment cycles. See 4.2 Recommended Dose and Dosage Adjustment.
Study Results
The efficacy of VYVGART was measured using the Myasthenia Gravis-Specific Activities of Daily Living scale (MG-ADL) which assesses the impact of gMG on daily functions of 8 signs or symptoms that are typically affected in gMG. Each item is assessed on a 4-point scale where a score of 0 represents normal function and score of 3 represents loss of ability to perform that function. A total score ranges from 0 to 24, with the higher scores indicating more impairment. In this study, an MG-ADL responder was defined as a patient with a 2-point or greater reduction in the total MG-ADL score compared to the treatment cycle baseline, for at least 4 consecutive weeks with the first reduction occurring no later than 1 week after the last infusion of the cycle.
The efficacy of VYVGART was also measured using the Quantitative Myasthenia Gravis (QMG) total score which is a 13-item categorical grading system that assesses muscle weakness. Each item is assessed on a 4-point scale where a score of 0 represents no weakness and a score of 3 represents severe weakness. A total possible score ranges from 0 to 39, where higher scores indicate more severe impairment. In this study, a QMG responder was defined as a patient who had a 3-point or greater reduction in the total QMG score compared to the treatment cycle baseline for at least 4 consecutive weeks, with the first reduction occurring no later than 1 week after last infusion of the cycle.
The primary efficacy endpoint was the comparison of the percentage of MG-ADL responders during the first treatment cycle between treatment groups in the AChR-Ab seropositive population. A key secondary endpoint was the comparison of the percentage of QMG responders during the first treatment cycle between both treatment groups in the AChR-Ab positive population. Results are shown in Table 4. This was also assessed in the overall population.
Table 4: Results of Key Endpoints in Cycle 1 of Study ARGX-113-1704 in AChR-Ab positive patients with Myasthenia Gravis (mITT analysis set)
| Primary & Key Secondary Endpoints | Population | Efgartigimod (n/N) (%) | Placebo (n/N) (%) | P-valuea | Difference Efgartigimod alfa-Placebo (95% CI)a |
| MG-ADL Responders | AChR-Ab seropositive | 44/65 (67.7) | 19/64 (29.7) | < 0.0001 | 38.0 (22.1; 54.0) |
| QMG Responders | AChR-Ab seropositive | 41/65 (63.1) | 9/64 (14.1) | < 0.0001 | 49.0 (34.5; 63.5) |
MG-ADL=Myasthenia Gravis Activities of Daily Living; AChR-Ab=acetylcholine receptor-antibody QMG=Quantitative Myasthenia Gravis; n=number of patients for whom the observation was reported; N=number of patients in the analysis set; CI=confidence interval; mITT=modified Intention to Treat
a Based on the difference in proportions
Figure 1 shows the mean change from baseline on the MG-ADL during cycle 1.
Figure 1: Mean Change From Baseline in Total MG-ADL Over Time During Cycle 1 in AChR-Ab Seropositive Patients (mITT Analysis Set)
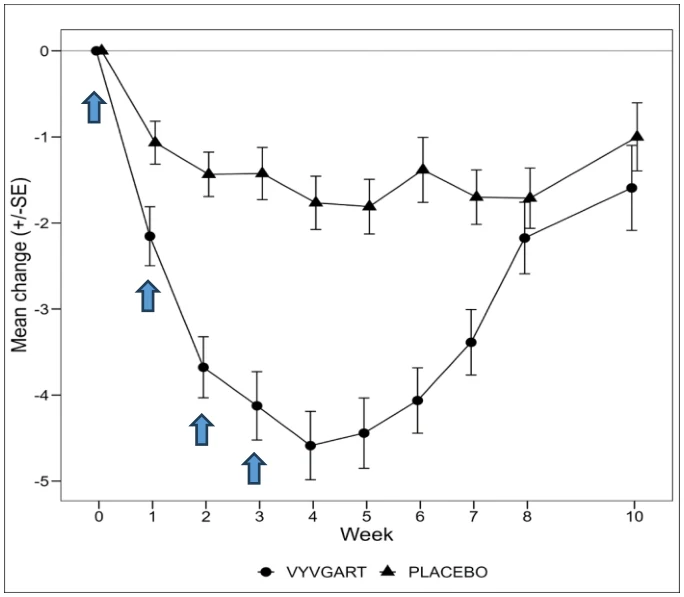
Note: the arrows indicate the visits where VYVGART or placebo were administered
In patients who responded to treatment, the duration of responder status was 5 weeks in 5/44 (11%) patients, 6 to 7 weeks in 14/44 (32%) of patients, 8 to 11 weeks in 10/44 (23%) patients and 12 weeks or more in 15/44 (34%) patients, in the AChR-Ab seropositive MG-ADL responders.
16 Non-Clinical Toxicology
General toxicology
In a 4-week repeat-dose toxicity study rats were treated with efgartigimod alfa at doses of 0 (0.9% sodium chloride solution), 10, 30, or 100 mg/kg administered by IV injection once every 2 days (total of 15 IV doses). Findings of Kupffer cell hypertrophy/hyperplasia was seen in male and female rat liver at 100 mg/kg that were considered of uncertain relationship to treatment. The no-observed-adverse effect-level (NOAEL) was established at 30 mg/kg, approximately 3 times the recommended human dose (RHD) of 10 mg/kg, on a body weight (mg/kg) basis.
In the pivotal 26-week toxicity study of efgartigimod alfa, cynomolgus monkeys received IV infusions at doses of 0 (vehicle), 10, 30, and 100 mg/kg once per week (total of 27 infusions). Enterocolitis was reported in 2 low-dose monkeys and 1 high-dose monkey, with greater severity observed at the high dose. The diarrhea observed in the high-dose monkey was accompanied by myeloid hyperplasia in the bone marrow of the sternum. Findings have uncertain relationship to treatment. The NOAEL was established at 100 mg/kg, approximately 10 times the human dose RHD of 10 mg/kg, on a body weight (mg/kg) basis.
Carcinogenicity
No studies have been conducted to assess the carcinogenic potential of efgartigimod alfa.
Genotoxicity
No studies have been conducted to assess the genotoxic potential of efgartigimod alfa.
Reproductive and developmental toxicology
Reproductive and development toxicity studies were conducted for efgartigimod alfa given by IV bolus injection once per day at doses of 0 (vehicle), 30, or 100 mg/kg in rats and rabbits. For all studies, the NOAEL was established at 100 mg/kg, approximately 10 times the RHD of 10 mg/kg, on a body weight (mg/kg) basis. Efgartigimod alfa concentrations in maternal milk and sera of fetuses or F1 offspring were not assessed. The potential effect of efgartigimod alfa on FcRn-mediated transfer of maternal antibodies to the fetus was not assessed.
A fertility study was conducted in male and female rats. Males were dosed from 4 weeks before mating and up to day 43 of the study, and females were dosed 2 weeks before mating and up to day 7 of gestation. Efgartigimod alfa did not adversely affect male and female fertility. The doses tested are 3 and 10 times the RHD of 10 mg/kg, on a body weight (mg/kg) basis.
An embryo-fetal development study was conducted in female rats and rabbits. Efgartigimod alfa was administered from gestation day 6 through 17 in rats and gestation day 6 through 28 in rabbits. There is no evidence of adverse developmental outcomes following the administration of efgartigimod alfa in rats and rabbits. In rabbits only, abortions were reported (2 in the low dose group, 1 in the high dose group) at an incidence that was comparable to historical control data of the test facility. These abortions were considered to be spontaneous occurrences. One low-dose rabbit presented with a contained liver lesion where an infectious cause could not be excluded. The doses tested are 3 and 10 times the RHD of 10 mg/kg, on a body weight (mg/kg) basis.
Female rats received efgartigimod alfa from day 6 of gestation to day 21 of lactation. Ataxia was observed in 4 F1 pups of 1 high-dose F0 female, with uncertain relationship to treatment. Overall, the results show that efgartigimod alfa had no effect on the pregnancy of the female rats, or on the development of both the pre- and postnatal F1 and F2 generation pups. The doses tested are 3 and 10 times the RHD of 10 mg/kg, on a body weight (mg/kg) basis.