


Product Monograph - 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 07/2025 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ...................................................................................................................... 4
1.2 Geriatrics ...................................................................................................................... 4
2 CONTRAINDICATIONS ...................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ...................................................................................... 5
4.1 Dosing Considerations .................................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ............................................................. 5
4.4 Administration .............................................................................................................. 6
5 OVERDOSAGE ................................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................................... 8
7 WARNINGS AND PRECAUTIONS ....................................................................................... 9
7.1 Special Populations ..................................................................................................... 11
7.1.1 Pregnant Women ....................................................................................................... 11
7.1.2 Breast-feeding ............................................................................................................ 11
7.1.3 Pediatrics .................................................................................................................... 11
7.1.4 Geriatrics ................................................................................................................... 11
8 ADVERSE REACTIONS .................................................................................................... 12
8.1 Adverse Reaction Overview ....................................................................................... 12
8.5 Post-Market Adverse Reactions ................................................................................. 12
9 DRUG INTERACTIONS .................................................................................................... 13
9.4 Drug-Drug Interactions ............................................................................................... 13
9.5 Drug-Food Interactions............................................................................................... 15
9.6 Drug-Herb Interactions ............................................................................................... 15
10 CLINICAL PHARMACOLOGY ............................................................................................ 15
10.1 Mechanism of Action................................................................................................. 15
10.2 Pharmacodynamics .................................................................................................... 15
10.3 Pharmacokinetics ....................................................................................................... 16
11 STORAGE, STABILITY AND DISPOSAL .............................................................................. 17
PART II: SCIENTIFIC INFORMATION ....................................................................................... 18
13 PHARMACEUTICAL INFORMATION ................................................................................. 18
15 MICROBIOLOGY ............................................................................................................ 18
16 NON-CLINICAL TOXICOLOGY .......................................................................................... 18
17 SUPPORTING PRODUCT MONOGRAPHS ......................................................................... 20
PATIENT MEDICATION INFORMATION .................................................................................. 21
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection (Lidocaine Hydrochloride and Dextrose Injection) by intravenous administration is indicated for:
- the treatment of ventricular tachycardia and premature ventricular beats of a life- threatening nature which may occur during cardiac manipulation such as surgery or catheterization or during acute myocardial infarction, digitalis toxicity or other cardiac diseases.
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is indicated when fluid restriction is desirable.
This drug requires administration by experienced health professionals, with emergency resuscitative equipment and drugs immediately available (see 7 WARNINGS AND PRECAUTIONS).
1.1 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
A reduction in dosage may be necessary for elderly patients, particularly those with compromised cardiovascular and/or hepatic function (see 7.1.4 WARNINGS AND PRECAUTIONS, Geriatrics).
2 CONTRAINDICATIONS
- 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
- Patients with known hypersensitivity to local anesthetics of the amide type, such as prilocaine, mepivacaine or bupivacaine, or to other components of the solution;
- Patients with Adams-Stokes syndrome, or severe degrees of sinoatrial, atrioventricular or intraventricular block.
- Patients with supraventricular arrhythmias.
- Patients with severe myocardial depression.
Solutions containing dextrose may be contraindicated in patients with known allergy to corn or corn products.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The onset of action following a single intravenous injection varies from 45 to 90 seconds. The duration of action is 10 to 20 minutes.
- No more than 200 to 300 mg of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection should be administered during a one hour period (see 7 WARNINGS AND PRECAUTIONS, 10.2 CLINICAL PHARMACOLOGY, Pharmacodynamics and 16 NON-CLINICAL TOXICOLOGY).
- Intravenous infusions should be terminated as soon as the patient's basic cardiac rhythm appears to be stable or at the earliest signs of toxicity. It is rarely necessary to continue intravenous infusion beyond 24 hours. As soon as possible, and when indicated, patients should be changed to an oral antiarrhythmic agent for maintenance therapy.
- Intravenous infusions of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection must be administered under constant ECG and blood pressure monitoring and with meticulous regulation of infusion rate, in order to avoid potential overdosage and toxicity.
4.2 Recommended Dose and Dosage Adjustment
Single Intravenous Injection
The usual dose is 50 to 100 mg 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection administered under ECG and blood pressure monitoring. This dose may be administered at the rate of approximately 25 to 50 mg/min. Sufficient time should be allowed to enable a slow circulation to carry the drug to the site of action. If the initial injection of 50 to 100 mg does not produce a desired response, a second dose may be repeated after 10 minutes. Elderly patients and those with congestive heart failure or cardiogenic shock may require smaller bolus doses.
Continuous Intravenous Infusion
Following intravenous injection, 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection may be administered by intravenous infusion at a rate of 1-2 mg/min (approximately 15-30 mcg/kg/min in the average 70 kg patient) in those patients in whom the arrhythmia tends to recur, and who are incapable of receiving oral antiarrhythmic therapy.
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection should be used only when fluid restriction is desirable.
When administering 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection by continuous intravenous infusion, it is necessary to use an infusion pump or a precision volume control I.V. set.
Health Canada has not authorized an indication for pediatric use (see 1.1 INDICATIONS, Pediatrics).
It is recommended that the administration set be replaced at least once every 24 hours.
Directions for Use of VIAFLEX Plastic Containers
Do not remove unit from overwrap until ready for use. The overwrap is a moisture barrier. The inner bag maintains the sterility of the product. After removing overwrap, check for leaks by firmly squeezing the inner bag. If leaks are found, discard solution as sterility may be impaired.
Visually inspect the container. If the administration port protector is damaged, detached, or not present, discard container as solution path sterility may be impaired.
Warning: Do not use plastic containers in series connections. Such use could result in air embolism due to residual air (approximately 15 mL) being drawn from the primary container before administration of the fluid from the secondary container is completed.
To Open
Tear overwrap down the side at the slit and remove solution container. Do not add supplementary medication.
Preparation for Administration
- 1. Suspend container from eyelet support.
- 2. Remove plastic protector from outlet port at bottom of container.
- 3. Attach administration set. Refer to complete directions accompanying set.
4.4 Administration
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is for intravenous administration (injection, infusion) only.
In the treatment of ventricular arrhythmias, an intravenous injection should be given initially, followed by an intravenous infusion.
When administering 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection, careful and constant monitoring of cardiovascular and respiratory vital signs and the patient's state of consciousness is required. At the first sign of change, oxygen should be administered.
5 OVERDOSAGE
Symptoms of idiosyncratic reactions are described under 8 ADVERSE REACTIONS.
Lidocaine toxicity may appear at serum concentrations greater than 8 mg/L.
Toxicity is initially manifested as CNS excitation and may result in a slow onset of nervousness, dizziness, delirium, blurred vision and tremors followed by drowsiness, convulsions, unconsciousness and possibly respiratory arrest.
Central nervous system toxicity is a graded response, with symptoms and signs of escalating severity. The first symptoms are circumoral paresthesia, numbness of the tongue, lightheadedness, hyperacusis and tinnitus. Visual disturbance and muscular tremors are more serious and precede the onset of generalized convulsions.
Unconsciousness and grand malconvulsions may follow, which may last from a few seconds to several minutes. Hypoxia and hypercarbia occur rapidly following convulsions due to the increased muscular activity, together with the interference with normal respiration. In severe cases apnea may occur.
Acidosis increases the toxic effects.
Cardiovascular toxic effects are generally preceded by signs of toxicity in the central nervous system, unless the patient is receiving a general anaesthetic or is heavily sedated with medicines such as a benzodiazepine or a barbiturate. Toxic cardiovascular reactions are usually depressant in nature, may occur rapidly and with little warning and can lead to peripheral vasodilation, severe hypotension, conduction defects, bradycardia, asystole, arrhythmias, including ventricular tachycardia/fibrillation, cardiovascular collapse which may lead, to cardiac arrest, apnea, seizures, coma, respiratory arrest and death. In rare cases, cardiac arrest has occurred without prodromal CNS effects.
Treatment of Overdose
Discontinue administration of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection. Maintain a patent airway and support ventilation with oxygen and assisted or controlled respiration as required. Should a convulsion persist despite ventilation therapy, small increments of a benzodiazepine (e.g. diazepam) or an ultra- short acting barbiturate (e.g. thiopentone) may be given intravenously, bearing in mind that anticonvulsant drugs may also depress respiration and the circulation. Use of intravenous lipid emulsion should be considered.
Cardiovascular depression may require circulatory assistance in the form of elevation of legs, intravenous fluids and/or vasopressor agents, volume expanders and, if necessary, cardiac massage.
Recovery is due to redistribution and metabolism of the drug. Recovery may be rapid unless large amounts of the drug (>5 mcg/mL) have been administered.
If the convulsions do not stop spontaneously in 15-20 seconds, an anticonvulsant should be given intravenously. Intravenous administration of thiopental 100-150 mg will abort the convulsions rapidly. Alternatively, diazepam 5-10 mg i.v. may be used, although its action is slower.
Hypotension may be counteracted by giving sympathomimetic drugs (e.g., epinephrine). Adrenergic agents of both α-adrenoceptor stimulating and β-adrenoceptor stimulating type are generally effective. The bradycardia may be treated with parasympatholytic agents.
Should circulatory arrest occur, immediate cardiopulmonary resuscitation should be instituted. Continued optimal oxygenation and ventilation and circulatory support as well as treatment of acidosis are of vital importance, since hypoxia and acidosis will increase the systemic toxicity of local anesthetics.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Intravenous | Solution: 4 mg / mL of lidocaine hydrochloride and 50 mg / mL of dextrose | Sodium hydroxide and water for injection |
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is supplied in VIAFLEX plastic containers, in the following sizes and concentrations:
250 mL
500 mL
0.4% Lidocaine Hydrochloride and 5% Dextrose solution
√
√
0.4% lidocaine hydrochloride provides 4 mg of lidocaine hydrochloride per mL.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Composition
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is a sterile, nonpyrogenic solution prepared from 0.4% Lidocaine Hydrochloride and Dextrose in Water for Injection. The solution serves as a cardiac antiarrhythmic agent intended for intravenous use. The pH range is 3.5 to 6.0. The pH is adjusted with sodium hydroxide.
7 WARNINGS AND PRECAUTIONS
General
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection requires administration by experienced healthcare professionals.
Constant ECG monitoring is essential for the proper administration of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection intravenously. Signs of excessive depression of cardiac conductivity, such as prolongation of PR interval and QRS complex, and the appearance of aggravation of arrhythmias, should be followed by prompt cessation of the intravenous infusion.
It is mandatory to have emergency resuscitative equipment and drugs immediately available to manage possible adverse reactions involving the cardiovascular, respiratory, or central nervous systems.
Anaphylactic reactions may occur following administration of lidocaine hydrochloride.
In emergency situations, when a ventricular rhythm disorder is suspected, and ECG equipment is not available, a single dose may be administered when the physician in attendance has determined that the potential benefits outweigh the possible risks. If possible, emergency resuscitative equipment and drugs should be available.
0.4% Lidocaine Hydrochloride and 5% Dextrose Injection should be used with caution in patients with:
- bradycardia,
- severe digitalis intoxication,
- first or second-degree heart block in the absence of a pacemaker
- hypokalaemia
- impaired hepatic function
- porphyria
- epilepsy
- impaired cardiac conduction
- impaired renal function
- severe shock
- cardiac decompensation
- hypotension
- posterior diaphragmal infarction with a tendency towards development of heart block.
Lower doses should be used in patients with congestive cardiac failure and following cardiac surgery.
Since CNS effects may not be apparent as an initial manifestation of toxicity, circulatory collapse should be monitored in unconscious patients.
Intravenous administration of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection is sometimes accompanied by a hypotensive response, and, in overdosage, this may be precipitous. For this reason the intravenous dose should not exceed 100 mg in a single injection, and no more than 200-300 mg in a one hour period (see 4 DOSAGE AND ADMINISTRATION). When high doses are used and the patient’s myocardial function is impaired, combination with other drugs which reduce the excitability of cardiac muscle requires caution.
Repeated doses of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection may cause significant increases in blood levels with each repeated dose because of slow accumulation of the drug or its metabolites. Tolerance to elevated blood levels varies with the status of the patient.
Debilitated, elderly patients and acutely ill patients should be given reduced doses commensurate with their age and physical condition. 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection should also be used with caution in patients with epilepsy, impaired cardiac conduction, bradycardia, impaired hepatic function or renal function and in severe shock.
Carcinogenesis and Mutagenesis
Long term studies in animals to evaluate the carcinogenic and mutagenic potential or the effect on fertility of lidocaine hydrochloride have not been conducted.
Cardiovascular
There have been reports of lidocaine-induced hypersensitivity reactions leading to Kounis syndrome. Kounis syndrome is a serious allergic reaction that includes acute coronary syndrome and can lead to myocardial infarction.
Hematologic
Theoretical evidence suggests that lidocaine may have porphyrogenic properties. The clinical significance of this is unknown. Caution should be exercised if intravenous lidocaine (0.4% Lidocaine Hydrochloride and 5% Dextrose Injection) is administered to patients with acute porphyria.
Hepatic/Biliary/Pancreatic
Patients with reduced hepatic blood flow or function have a longer lidocaine half-life and lower clearance and may therefore require a reduction in dosage.
Caution should be employed in the repeated use of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection in patients with severe liver disease, since possible accumulation of lidocaine or its metabolites may lead to toxic phenomena.
Renal
Impairment of renal function is unlikely to affect lidocaine clearance in the short term (24 hours).
However, toxicity due to accumulation of lidocaine and its metabolites may develop with prolonged or repeated administration.
Caution should be employed in the repeated use of 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection in patients with severe renal disease, since possible accumulation of lidocaine or its metabolites may lead to toxic phenomena.
Reproductive Health: Female and Male Potential
Fertility
Studies of lidocaine in animals to evaluate the effect on fertility have not been conducted.
7.1 Special Populations
7.1.1 Pregnant Women
Lidocaine crosses the placenta. Animal studies have revealed no evidence of harm to the fetus. Although lidocaine has been used extensively for surgical procedures during pregnancy with no reports of ill effects to mother or fetus, there are no adequate and well-controlled studies in pregnant women of the effects of lidocaine on the developing fetus. 0.4% Lidocaine Hydrochloride and 5% Dextrose Injection should not be administered during pregnancy, particularly at early stage, unless the benefits are considered to outweigh the risks.
7.1.2 Breast-feeding
Lidocaine passes into breast milk. One case report calculated that breastmilk contained
~40% of the maternal serum concentration after two boluses and seven hours of infusion, potentially resulting in a dose up to ~1.5 mg of lidocaine per day in the infant. The amount of lidocaine appearing in breast milk from the nursing mother receiving parenteral lidocaine is therefore unlikely to lead a significant accumulation of the parent drug in the breast fed infant. The remote possibility of an idiosyncratic or allergic reaction in the breast fed infant from lidocaine remains to be determined.
7.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
A reduction in dosage may be necessary for elderly patients, particularly those with compromised cardiovascular and/or hepatic function and/or prolonged infusion. The doses should be adjusted individually to the patients’ age and body weight. Dosages may need adaptation as cardiac output and hepatic blood flow decrease with advanced age indicating a decreased clearance of lidocaine.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse experiences following the administration of lidocaine are similar in nature to those observed with other amide type agents. These adverse experiences are, in general, dose- related and may result from high plasma levels caused by excessive dosage or rapid absorption, or may result from a hypersensitivity, idiosyncrasy or diminished tolerance on the part of the patient.
Common adverse reactions are those from the central and peripheral nervous system. They occur in 5-10% of the patients and are mostly dose-related.
8.5 Post-Market Adverse Reactions
Systemic reactions of the following types have been reported from post-marketing data:
Cardiovascular System
Rare cardiovascular manifestations are usually depressant and are characterized by bradycardia, hypotension, asystole and cardiovascular collapse which may lead to cardiac arrest. Arrhythmias, including ventricular tachycardia/ventricular fibrillation have also been reported.
There have been reports of lidocaine-induced hypersensitivity reactions leading to Kounis syndrome.
Central Nervous System
CNS manifestations are excitatory and/or depressant. Common adverse reactions are circumoral paresthesia, dizziness and drowsiness. Rare adverse reactions would include: persistent dizziness, lightheadedness, nervousness, apprehension, euphoria, confusion, hyperacusis, tinnitus, blurred vision, vomiting, and sensations of heat, cold or numbness, twitching, tremors, convulsions, unconsciousness, apnea, respiratory depression and arrest. The excitatory manifestations may be very brief or may not occur at all, in which case the first manifestation of toxicity may be drowsiness merging into unconsciousness and respiratory arrest.
Drowsiness following the administration of lidocaine is usually an early sign of a high lidocaine plasma level and may occur as a consequence of rapid absorption.
Hematologic System
Very rarely, neonatal methaemoglobinaemia can occur (see 7 WARNINGS AND PRECAUTIONS).
Methemoglobinemia was also reported in adults.
Immune System
Allergic reactions, including anaphylactic reactions, are characterized by cutaneous lesions, urticaria, edema, or in the most severe and very rare instances, hypersensitivity including anaphylactic shock. Allergic reactions of the amide type are rare and may occur as a result of sensitivity either to the drug itself, or to other components of the formulation.
Idiosyncratic reactions have been reported at low doses in some patients. Cross-sensitivity between Lidocaine Hydrochloride Injection and procainamide or Lidocaine Hydrochloride Injection and quinidine have not been reported.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Lidocaine is mainly metabolized in the liver by CYP1A2 and CYP3A4 (see 10.3 Pharmacokinetics). Since the affinity of lidocaine to CYP1A2 and CYP3A4 is very low compared to therapeutic plasma concentrations, it is less likely that the metabolism of substrates for these enzymes will be inhibited when coadministered with lidocaine. However, there is a potential for influence of other drugs on the plasma levels/effect of lidocaine, e.g. strong inhibitors or inducers of CYP1A2 and/or CYP3A4 and drugs that affect liver blood flow (see Table 2).
Table 2 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Proper/Common name | Source of Evidence | Effect | Clinical Comment |
| Proper/Common name | Source of Evidence | Effect | Clinical Comment |
| Amiodarone | CT, C | Like cimetidine, amiodarone has an unspecific inhibitory effect on CYP mediated metabolism. Concomitant administration has resulted in increased plasma levels of lidocaine and may result in toxic effects. | Therefore, concomitant administration with lidocaine should be avoided. If not possible, close monitoring and dose adjustment of lidocaine and/or amiodarone may be required. |
| Beta-blockers (propranolol, metoprolol, nadolol) | CT | Propranolol, metoprolol, and nadolol have been reported to reduce intravenous lidocaine clearance, probably through effects on hepatic blood flow and/or metabolism and may increase the plasma concentration of lidocaine by about 30%, less with metoprolol. | Therefore, concomitant administration of beta-blockers with lidocaine should be avoided. If not possible, close monitoring and dose adjustment may be required. |
| Cimetidine | CT | Cimetidine has an unspecific inhibitory effect on CYP (including CYP1A2 and CYP 3A4) mediated metabolism and reduces hepatic blood flow. Clinical experiments showed that the concomitant administration of cimetidine reduces the systemic clearance of lidocaine and increases lidocaine serum concentration by as much as 50%. Thus, therapeutic serum levels of lidocaine may rise to toxic levels when cimetidine is used concomitantly. Ranitidine has not displayed this effect. | Therefore, concomitant administration with lidocaine should be avoided. If not possible, close monitoring and dose adjustment of lidocaine and/or cimetidine may be required. |
CYP1A2 inducers (Phenytoin) | T | During concomitant administration of lidocaine and CYP1A2 inducers, plasma levels/effect of lidocaine may decrease. | Higher dose of lidocaine may be required. |
| CYP3A4 inducers (carbamazepine, phenobarbital, phenytoin, primidone) | CT | Concomitant administration with carbamazepine, phenobarbital, phenytoin, and primidone, may slightly decrease plasma levels of lidocaine (<10%). | No dose adjustment seems required. |
Strong inhibitors of CYP1A2 (fluvoxamine) | CT | Coadministration of fluvoxamine reduced [41%] the elimination of lidocaine in healthy subjects. Given concomitantly with lidocaine, strong inhibitors of CYP1A2 can cause a metabolic interaction leading to increased lidocaine plasma concentrations. | Therefore, coadministration of lidocaine should be avoided in patients treated with strong inhibitors of CYP1A2, such as fluvoxamine. |
Strong inhibitors of CYP3A4 (erythromycin, itraconazole) | CT | Erythromycin and itraconazole have each been shown to have modest or no effect on the pharmacokinetics of intravenous lidocaine (0-18% decreased elimination with erythromycin but no effect with itraconazole). | No dose adjustment seems required. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The mode of action of the antiarrhythmic effect of Lidocaine Hydrochloride Injection appears to be similar to that of procaine, procainamide, and quinidine. Ventricular excitability is depressed and the stimulation threshold of the ventricle is increased during diastole. The sinoatrial node is, however, unaffected. In contrast to the latter three drugs, Lidocaine Hydrochloride Injection in therapeutic doses does not produce a significant decrease in arterial pressure or in cardiac contractile force. In larger doses, Lidocaine Hydrochloride Injection may produce circulatory depression, but the magnitude of the change is less than that found with comparable doses of procainamide. Neither drug appreciably affects the duration of the absolute refractory period.
10.2 Pharmacodynamics
Lidocaine hydrochloride is a well-known anesthetic agent which has been used for many years for regional and topical anesthesia. However, it has been demonstrated to exert an antiarrhythmic effect by increasing the electrical stimulation threshold of the ventricle during diastole.
In decerebrated, vagotomised cats with stellate ganglia destroyed, lidocaine hydrochloride intravenous suppressed cardiac arrhythmias induced by faradic stimulation, barium chloride and epinephrine. The minimal effective dose was 0.5 mg per kg. This was 4 and 5 times less than the minimal doses of procaine and procainamide respectively.
In anesthetized open-chest dogs, lidocaine hydrochloride 5 mg per kg intravenously reduced the duration of methacholine-induced auricular arrhythmias by 55.5%. The effect of quinidine sulphate at the same dose was a reduction 46.5%. Ventricular arrhythmias induced by coronary ligation were controlled by total intravenous doses of 50 mg/kg. Convulsions and vomiting were produced and death occurred in 1 of 6 dogs at 75.5 mg/kg. In the same preparation, interruption of the arrhythmia was obtained by an injection of 15 mg/kg directly into the ventricle. In normothermic or hypothermic dogs the same effect was obtained in ventricular fibrillation induced by mechanical stimulation.
In anesthetized dogs, intravenous infusions of 40-80 mg converted digitalis-induced ventricular arrhythmia to sinus rhythm. Also, acetylstrophanthidin-induced ventricular tachycardia was suppressed at a minimal effective dose of lidocaine hydrochloride of 1 mg/kg intravenously.
Digitalis-induced ventricular tachycardia, which failed to respond to electro- shock was converted to normal sinus rhythm by intravenous injection of lidocaine hydrochloride 100 mg and ventricular tachycardia, induced by ouabain, was converted to supraventricular tachycardia by intravenous injection of 1-2 mg/kg.
In unanesthetized dogs with ventricular arrhythmia induced by coronary occlusion, intravenous injections of 5-10 mg/kg suppressed the arrhythmia. This effect could be maintained by intravenous infusion with calculated lidocaine hydrochloride blood levels of 1-3 mcg/mL.
Other effects in anesthetized intact dogs were depression of myocardial contractile force, heart rate and femoral arterial pressure with lidocaine hydrochloride 0.5 to 6 mg/kg intravenously. At 2.0 mg/kg intra-arterially the same effects were obtained but there was less diminution of contractile force. In both anesthetized and conscious dogs, lidocaine hydrochloride in rapid intravenous injection of 2, 4 and 8 mg/kg caused transient decrease of systolic arterial pressure, venous pressure, cardiac output, mean ejection rate, rate of development of arterial pressure, stroke work and calculated peripheral resistance. Heart rate was slightly increased. Effects were greatest at 8 mg/kg and were more pronounced and of longer duration in anesthetized dogs. There was return to basal levels in 3-5 minutes.
10.3 Pharmacokinetics
The pharmacokinetics of lidocaine hydrochloride has been studied in normal subjects and in patients.
Following a single intravenous injection, or termination of a continuous intravenous infusion, declining plasma concentration follows a biphasic curve. Plasma half-lives of 8 to 15 minutes have been reported for the initial phase. Various studies have reported the mean half-life at the terminal phase to be in the range 1.2 to 1.9 hours. The minimum effective antiarrhythmic plasma concentration of lidocaine hydrochloride has been reported to be in the range of 1.0 to 1.2 mcg /mL; concentrations higher than 5-6 mcg/mL are associated with an increased risk of toxicity.
Lidocaine is mainly metabolized in the liver by CYP1A2 and CYP3A4 to its two major metabolites, monoethylglycinexylidine (MEGX) and glycinexylidine (GX), both of which are pharmacologically active. Lidocaine has a high hepatic extraction ratio. Only a small fraction (3%) of lidocaine is excreted unchanged in the urine. The hepatic clearance of lidocaine is expected to depend largely on blood flow.
Absorption:
In rats which received 14C-labelled lidocaine hydrochloride by intravenous injection, rapid uptake by all tissues was noted. Tissue distribution studies in monkeys have indicated: high affinity for lung, spleen, kidney, stomach and adipose tissue; moderate affinity for brain and most gastrointestinal organs; and low affinity for musculoskeletal tissue and skin. Similar distribution has been observed in the dog.
Distribution:
Studies on plasma binding in monkey and man have indicated approximately 60% plasma binding within the plasma concentration range usually seen in clinical use. However, plasma binding was markedly reduced at concentrations of lidocaine hydrochloride exceeding 10 mcg/mL, presumably due to saturation of the binding sites.
Metabolism:
Studies in rabbit and rat have demonstrated that the liver is the principal site of metabolism. In man, hepatic clearance studies have shown that approximately 70% of the lidocaine hydrochloride passing through the liver was extracted. Microsomal enzyme systems are primarily responsible for hepatic metabolism. The major degradative pathway appears to be by conversion to monoethylglycinexylidide, followed by hydrolysis to 2,6,-xylidine; further conversion to 4-hydroxy-2,6-xylidine appears to occur in man.
Elimination:
Up to 10% of administered lidocaine hydrochloride may be excreted in the urine as unchanged drug. Although biliary secretion and intestinal absorption of lidocaine hydrochloride metabolites have been reported in rats, there is no evidence of biliary secretion in man.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15oC to 25oC).
For single use only. Discard unused portion.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Lidocaine hydrochloride
Chemical Name: 2-(Diethylamino)-2',6'-acetoxylidide monohydrochloride anhydrous
Molecular formula and molecular mass: C14H22N2O.HCl and 270.82 g/mol
Structural Formula:
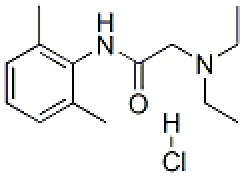
Physicochemical properties: Lidocaine hydrochloride is a white, odourless, crystalline powder which has a slightly bitter taste. It is very soluble in water and in alcohol, soluble in chloroform, and insoluble in ether.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
Table 3 – Median Lethal Dose Levels for Lidocaine Hydrochloride in Animals
SPECIES
SEX
ROUTE
LD50 (mg/kg)
mice
F
i.v.
17.9 mice
F
i.p.
164 mice
F
i.m.
200 mice
M
i.m.
154 rat
F
i.v.
19.7 rat
M
i.v.
21.4 dog
M & F
i.m.
100 guinea pig
F
i.m.
73
guinea pig
M
i.m.
67
rabbit
M
i.m.
450
Acute intravenous studies were performed in rabbits which received six serial injections of 1, 2, 3, 4 or 5 mg/kg at 15 minute intervals. At the 2 mg/kg dose level, slight depression was seen, beginning with the third injection. At 3 mg/kg there was depression and rigid extension of limbs after the last 5 injections. At 5 mg/kg there was severe depression and rigid limb extension after each injection; loss of righting reflex and convulsions began with the second injection and there was gasping for breath after each of the last injections.
Dogs were given intravenous incremental doses at 30 minute intervals until death occurred. Doses of 0.1 to 3.0 mg/kg were tolerated with minimal CNS or cardiovascular effects.
Convulsions, mydriasis, salivation, urination and defecation were observed after 10 mg/kg.
Respiratory arrest and death occurred in one dog after 30 mg/kg; cardiovascular collapse, respiratory arrest and death occurred in remaining animals after 100 mg/kg. Mean arterial blood pressure and heart rate increased briefly, beginning at 3.0 mg/kg, and decreased after 100 mg/kg. Myocardial conduction time was not significantly changed prior to 100 mg/kg administration.
Acute local responses were studied in rats and rabbits following single intramuscular injections of 2%, 4%, 6%, 8% and 10% solutions of lidocaine hydrochloride. Microscopic examination revealed inflammatory changes with all solutions. In general, reactions produced by 2% solutions were least, although lesions seen with all other concentrations were of similar degree. In rabbits sacrificed seven days after intramuscular administration, there was evidence of marked muscle fiber regeneration; after 30 days there was virtually complete resolution of inflammatory changes at the site of injection.
Subacute Toxicity
In one study, dogs received daily intravenous injections according to the following schedule:
0.1 mg/kg for 7 days, 0.3 mg/kg for 7 days, 1 mg/kg for 7 days and 3 mg/kg for 21 days. Mild transient convulsions were seen in one dog at the high dose level. No other signs of toxicity were observed. Gross and microscopic examination at autopsy did not reveal any drug related effects.
In a second study, dogs received daily intravenous injections of 2.5, 5 or 10 mg/kg for 28 days. No overt symptoms were observed at the low dose level. At the 5 mg/kg level there was transient sedation, ataxia, head tremor, prostration and emesis. At the 10 mg/kg level there were severe tremors, muscular weakness, ataxia, prostration and convulsions, although animals recovered within 5-10 minutes. No ECG or hemochemistry changes were seen. No evidence of drug-related pathology was seen at autopsy. Injection sites showed inflammatory changes in drug and saline- treated animals.
In rats which received daily intravenous doses of 1.5, 4.5 or 15.0 mg/kg for 14 days, overt effects were observed only at the 15.0 mg/kg level, at which convulsions and death occurred. Increased blood glucose levels were seen in male rats at all dose levels. At autopsy, no changes were attributed to drug treatment. Mild inflammatory changes were seen at injection sites.
Carcinogenicity:
Studies of lidocaine in animals to evaluate the carcinogenic potential have not been conducted.
Genotoxicity:
Studies of lidocaine in animals to evaluate the mutagenic potential have not been conducted.
Reproductive and Developmental Toxicology:
Studies of lidocaine in animals to evaluate the effect on fertility have not been conducted.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. XYLOCARD® (Solution, 20 mg/mL of lidocaine hydrochloride), submission control 288946, Product Monograph, Aspen Pharmacare Canada Inc. (DEC 19, 2024)