


Product Monograph - AA-Levocarb CR
RECENT MAJOR LABEL CHANGES
| None | N/A |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ..................................................................................................................... 4
1.2 Geriatrics ..................................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ................................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ............................................................ 6
4.4 Administration ............................................................................................................. 8
4.5 Missed Dose ................................................................................................................ 8
5 OVERDOSAGE .............................................................................................................. 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 9
7 WARNINGS AND PRECAUTIONS.................................................................................... 9
7.1 Special Populations ................................................................................................... 12
7.1.1 Pregnant Women: ................................................................................................... 12
7.1.2 Breast-feeding ......................................................................................................... 12
7.1.3 Pediatrics ................................................................................................................. 12
7.1.4 Geriatrics ................................................................................................................. 12
8 ADVERSE REACTIONS ................................................................................................. 12
8.1 Adverse Reaction Overview ...................................................................................... 12
8.2 Clinical Trial Adverse Reactions ................................................................................. 12
8.3 Less Common Clinical Trial Adverse Reactions ......................................................... 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data ...................................................................................................... 15
8.5 Post-Market Adverse Reactions ................................................................................ 15
9 DRUG INTERACTIONS ................................................................................................. 16
9.1 Serious Drug Interactions .......................................................................................... 16
9.2 Drug Interactions Overview ...................................................................................... 16
9.3 Drug-Behavioural Interactions .................................................................................. 16
9.4 Drug-Drug Interactions .............................................................................................. 16
9.5 Drug-Food Interactions ............................................................................................. 19
9.6 Drug-Herb Interactions .............................................................................................. 19
9.7 Drug-Laboratory Test Interactions ............................................................................ 19
10 CLINICAL PHARMACOLOGY ........................................................................................ 19
10.1 Mechanism of Action ................................................................................................ 19
10.2 Pharmacodynamics ................................................................................................... 19
10.3 Pharmacokinetics ...................................................................................................... 21
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 23
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 23
PART II: SCIENTIFIC INFORMATION ...................................................................................... 24
13 PHARMACEUTICAL INFORMATION ............................................................................. 24
14 CLINICAL TRIALS ......................................................................................................... 25
14.1 Clinical Trials by Indication ........................................................................................ 25
14.2 Comparative Bioavailability Studies .......................................................................... 25
15 MICROBIOLOGY ......................................................................................................... 28
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 28
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 30
PATIENT MEDICATION INFORMATION ................................................................................. 31
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
AA-LEVOCARB CR (levodopa and carbidopa controlled-release tablets) is indicated for the treatment of Parkinson's disease.
AA-LEVOCARB CR is not recommended for the treatment of drug-induced extrapyramidal reactions.
1.1 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of AA-LEVOCARB CR in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience with levodopa/carbidopa combinations suggest that use in the geriatric population is not associated with differences in safety or effectiveness (see 4.2 Recommended Dose and Dosage Adjustment)
2 CONTRAINDICATIONS
AA-LEVOCARB CR are contraindicated in patients:
- who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- taking non-selective monoamine oxidase inhibitors (MAOIs). These inhibitors must be discontinued at least two weeks prior to initiating therapy with AA-LEVOCARB CR. AA-LEVOCARB CR may be administered concomitantly with a MAO inhibitor with selectivity for MAO type B (e.g. selegiline HCl) (see 9.4 Drug-Drug Interactions) at the manufacturer’s recommended dose which maintains selectivity for MAO type B.
- with clinical or laboratory evidence of uncompensated cardiovascular, endocrine, hematologic, hepatic, pulmonary (including bronchial asthma), or renal disease.
- with narrow angle glaucoma.
- for whom administration of a sympathomimetic amine is contraindicated (e.g., epinephrine, norepinephrine, amphetamines or isoproterenol).
- with suspicious, undiagnosed skin lesions or a history of melanoma; because levodopa may activate a malignant melanoma.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The daily dosage of AA-LEVOCARB CR must be determined by careful titration (see 4.2 Recommended Dose and Dosage Adjustment, Titration).
- Patients should be monitored closely during the dose adjustment period, particularly with regard to appearance or worsening of nausea or abnormal involuntary movements, including dyskinesias, chorea and dystonia.
- Standard antiparkinson drugs, other than levodopa alone, may be continued while AA-LEVOCARB CR is being administered although their dosage may have to be adjusted. The delayed onset of action with AA-LEVOCARB CR may require the supplemental use of conventional levodopa/carbidopa immediate-release tablets s for optimal control in the mornings.
- When patients are receiving levodopa monotherapy or levodopa/carbidopa immediate-release tablets, this medication must be discontinued at least 8 hours before therapy with AA-LEVOCARB CR is started.
4.2 Recommended Dose and Dosage Adjustment
General
- AA-LEVOCARB CR tablets contain a 4:1 ratio of levodopa to carbidopa. AA-LEVOCARB CR 200 mg/50 mg contains levodopa 200 mg/carbidopa 50 mg per tablet. AA-LEVOCARB CR 100 mg/25 mg contains levodopa 100 mg/carbidopa 25 mg per tablet.
Adults
Initial Dosage and Titration for Patients Currently Treated with Conventional Levodopa/Carbidopa Combinations:
- Dosage with AA-LEVOCARB CR 200 mg/50 mg should be substituted at an amount that eventually provides approximately 10 to 30 percent more levodopa per day. The interval between doses should be prolonged by 30 to 50 percent. Initially, patients should receive AA-LEVOCARB CR 200 mg/50 mg at a dosage that provides the same amount of levodopa, but with a longer dosing interval. Depending on clinical response, the dosage may be increased. A guide for the initiation of treatment with AA-LEVOCARB CR 200 mg/50 mg is shown in the following table:
Table 1 - Guideline for initial conversion from levodopa/carbidopa immediate-release tablets to AA-LEVOCARB CR 200 mg/50 mg
| Levodopa/carbidopa immediate-release tablets | AA-LEVOCARB CR |
| Total Daily Dose* Levodopa (mg) | Suggested Dosage Regimen |
| 300 - 400 | 1 tablet 200 mg/50 mg b.i.d. |
| 500 - 600 | 1 tablet 200 mg/50 mg plus 1 tablet 100 mg/25 mg b.i.d. or 1 tablet 200 mg/50 mg t.i.d. |
| Levodopa/carbidopa immediate-release tablets | AA-LEVOCARB CR |
| Total Daily Dose* Levodopa (mg) | Suggested Dosage Regimen |
| 700 - 800 | 1 tablet 200mg/50mg plus 1 tablet 100mg/25mg, in the a.m., 1 tablet 200mg/50mg plus 1 tablet 100mg /25mg, in the early p.m., 1 tablet 200mg /50mg, in the later p.m. |
| 900 - 1000 | 2 tablets 200mg /50mg, in the a.m. 2 tablets 200mg /50mg, in the early p.m. 1 tablet 200mg /50mg in the later p.m. |
* For dosing ranges not shown in the table, see 4.2 Recommended Dose and Dosage Adjustment
- AA-LEVOCARB CR 100 mg/25 mg is available to facilitate titration when 100 mg steps are required and as an alternative to the half tablet of AA-LEVOCARB CR 200 mg/50 mg tablets.
Initial Dosage for Patients Currently Treated with Levodopa Alone:
- Levodopa must be discontinued at least eight hours before therapy with AA-LEVOCARB CR 200 mg/50 mg is started. AA-LEVOCARB CR should be substituted at a dosage that will provide approximately 25% of the previous levodopa dosage. In patients with mild to moderate disease, the initial dose is usually 1 tablet of AA-LEVOCARB CR 200 mg/50 mg two times daily.
Initial Dosage for Patients Without Prior Levodopa Therapy:
- AA-LEVOCARB CR 100 mg/25 mg tablets may be used in early-stage patients who have not had prior levodopa therapy or to facilitate titration when necessary in patients receiving AA-LEVOCARB CR 200 mg/50 mg tablets. The initial recommended dose is 1 tablet of AA-LEVOCARB CR 100 mg/25 mg twice daily. For patients who require more levodopa, a daily dose of 1 to 4 tablets of AA-LEVOCARB CR 100 mg/25 mg twice a day is generally well-tolerated.
- When appropriate, levodopa therapy may also be initiated with AA-LEVOCARB CR 200 mg/50 mg. The initial recommended dose in patients with mild to moderate disease is 1 tablet of AA-LEVOCARB CR 200 mg/50 mg two times daily. Initial dosages should not exceed 600 mg per day of levodopa or be given at intervals of less than 6 hours.
Titration:
Doses and dosing intervals must be adjusted on an individual basis, depending upon therapeutic response. An interval of at least 3 days between dosage adjustments is recommended. Most patients have been adequately treated with 2 to 8 levodopa/carbidopa
- controlled-release tablets 200 mg/50 mg per day, administered as divided doses at intervals ranging from 4 to 12 hours during the waking day.
- If the divided doses of AA-LEVOCARB CR 200 mg/50 mg are not equal, it is recommended that the smaller doses be given at the end of the day.
Maintenance:
- Because Parkinson's disease is progressive, periodic clinical evaluations are recommended and adjustment of the dosage regimen of AA-LEVOCARB CR may be required.
Discontinuation:
- Patients should be observed carefully if abrupt reduction or discontinuation of AA-LEVOCARB CR is required, especially if the patient is receiving neuroleptics 7 WARNINGS AND PRECAUTIONS, Neurologic, Neuroleptic Malignant Syndrome).
- If general anesthesia is required, AA-LEVOCARB CR may be continued as long as the patient is permitted to take oral medication. If therapy is interrupted temporarily, the usual dosage should be administered as soon as the patient is able to take oral medication.
Pediatrics (<18 years of age)
- Health Canada has not authorized an indication for pediatric use.
Geriatrics (>65 years of age)
- Doses for all patients including geriatric population are individually adjusted by titration (see 4.1 Dosing Considerations; 4.2 Recommended Dose and Dosage Adjustment, Adults).
4.4 Administration
- AA-LEVOCARB CR 200 mg/50 mg may be administered as a whole or as half tablets.
- AA-LEVOCARB CR 100 mg/25 mg should only be administered as whole tablets.
- To maintain the controlled-release properties of the product, tablets should not be chewed or crushed.
Addition of Other Antiparkinsonian Medications
- Anticholinergic agents, dopamine agonists, amantadine and lower doses of selective MAO-B inhibitors can be given with levodopa/carbidopa controlled-release tablets. When combining therapies, dosage adjustments may be necessary.
4.5 Missed Dose
If a dose is missed, it should be taken as soon as possible. If it is almost time to take the next dose, the missed dose should not be taken, and the normal schedule should be resumed.
5 OVERDOSAGE
Management of acute overdosage with AA-LEVOCARB CR is basically the same as management of acute overdosage with levodopa; however, pyridoxine is not effective in reversing the actions of AA-LEVOCARB CR.
Electrocardiographic monitoring should be instituted and the patient observed carefully for the development of arrhythmias; if required, appropriate antiarrhythmic therapy should be given. The possibility that the patient may have taken other drugs as well as levodopa/carbidopa controlled-release tablets should be taken into consideration. To date, no experience has been reported with dialysis; hence, its value in overdosage is not known.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Controlled-release tablet 100 mg/25 mg Levodopa /carbidopa | Hydroxypropyl methylcellulose, magnesium stearate, red ferric oxide |
| Oral | Controlled-release tablet 200 mg/50 mg Levodopa /carbidopa | Hydroxypropyl methylcellulose, magnesium stearate, yellow ferric oxide |
AA-LEVOCARB CR is a controlled-release formulation of levodopa and carbidopa, in a ratio of 4:1. The tablet contains a polymer-based drug delivery system which controls the release of levodopa and carbidopa as it slowly erodes.
AA-LEVOCARB CR 100 mg/25 mg: Each oval, pink, biconvex tablet engraved "100" over "25" on one side, contains 100 mg of levodopa and 25 mg of anhydrous carbidopa. Available in bottles of 100 tablets.
AA-LEVOCARB CR 200 mg/50 mg: Each oval, peach, biconvex tablet scored and engraved "200" over "50" on one side, contains 200 mg of levodopa and 50 mg of anhydrous carbidopa. Available in bottles of 100 tablets.
7 WARNINGS AND PRECAUTIONS
See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Physical Activity: Patients who improve while on therapy with AA-LEVOCARB CR should increase physical activities gradually, with caution, consistent with other medical considerations such as the presence of osteoporosis or phlebothrombosis.
Cardiovascular
Care should be exercised in administering AA-LEVOCARB CR to patients with a history of recent myocardial infarction who have residual atrial, nodal, or ventricular arrhythmias. In such patients, cardiac function should be monitored with particular care during the period of initial dosage administration and titration, in a facility with provisions for intensive cardiac care.
Driving and Operating Machinery
Psychomotor Performance: Certain side effects that have been reported with AA-LEVOCARB CR may affect some patients’ ability to drive or operate machinery.
Given the reported cases of somnolence and sudden onset of sleep (not necessarily preceded by somnolence), physicians should caution patients about the risk of operating hazardous machinery, including driving motor vehicles, while taking AA-LEVOCARB CR. If drowsiness or sudden onset of sleep should occur, patients should be informed to refrain from driving or operating machines and to immediately contact their physician (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Gastrointestinal
AA-LEVOCARB CR should be administered cautiously to patients with a history of peptic ulcer disease due to the possibility of upper gastrointestinal hemorrhage.
Monitoring and Laboratory Tests
Periodic evaluations of hepatic, hematopoietic, cardiovascular and renal function are recommended during extended therapy with AA-LEVOCARB CR (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data).
AA-LEVOCARB CR may cause a false-positive reaction for urinary ketone bodies when a tape test is used for determination of ketonuria. False-negative tests may result with the use of glucose-oxidase methods of testing for glucosuria. Caution should be exercised when interpreting the plasma and urine levels of catecholamines and their metabolites in patients on levodopa or levodopa/carbidopa therapy (see 9.7 Drug-Laboratory Test Interactions).
Neurologic
Dyskinesia: As with levodopa or levodopa/carbidopa immediate-release tablets, AA-LEVOCARB CR may cause involuntary movements and mental disturbances. These reactions are thought to be due to increased brain dopamine following administration of levodopa. These adverse reactions may be more prolonged with AA-LEVOCARB CR than with levodopa/carbidopa immediate-release tablets.
Seizures: AA-LEVOCARB CR should be used cautiously in patients who have a history of seizures or have conditions associated with seizure or have a lowered seizure threshold.
Neuroleptic Malignant Syndrome: A symptom complex resembling the neuroleptic malignant syndrome including muscular rigidity, elevated body temperature, altered consciousness, mental changes, autonomic instability and increased serum creatine phosphokinase has been reported in association with rapid dose reduction, withdrawal of, or changes in antiparkinsonian therapy. Therefore, patients should be observed carefully when the dosage of AA-LEVOCARB CR is reduced abruptly or discontinued, especially if the patient is receiving neuroleptics.
Ophthalmologic
Glaucoma: Patients with chronic wide angle glaucoma may be treated cautiously with AA-LEVOCARB CR (levodopa and carbidopa), provided the intraocular pressure is well controlled and the patient monitored carefully for changes in intraocular pressure during therapy. AA-LEVOCARB CR is contraindicated in patients with narrow angle glaucoma (see 2 CONTRAINDICATIONS).
Peri-Operative Considerations
If general anesthesia is required, AA-LEVOCARB CR may be continued as long as the patient is permitted to take oral medication. If therapy is interrupted temporarily, the usual dosage should be administered as soon as the patient is able to take oral medication (see 4.2 Recommended Dose and Dosage Adjustment, Discontinuation).
Psychiatric
Depression: All patients should be observed carefully for the development of depression with concomitant suicidal tendencies. Patients with past or current psychoses should be treated with caution.
Behavioural Changes: Patients and caregivers should be advised to adhere to dosage instructions given by the physician. Patients should be regularly monitored for the development of impulse control disorders. Patients and caregivers should be made aware that behavioral symptoms of impulse control disorders, including pathological (compulsive) gambling, hypersexuality, increased libido, compulsive spending/buying, and binge/compulsive eating, have been reported in patients treated with dopaminergic agonists and/or other dopaminergic treatments for Parkinson's disease, including AA-LEVOCARB CR (see 8.5 Post-Market Adverse Reactions). Literature and post marketing reports have described a very rare addictive pattern of dopamine replacement therapy, in which patients use doses in excess of those required to control their motor symptoms. Review of treatment is recommended if such symptoms develop.
Hallucinations: Hallucinations and confusion are known side effects of treatment with dopaminergic agents, including levodopa. Patients should be aware of the fact that hallucinations (mostly visual) can occur.
Skin
Melanoma: Epidemiological studies have shown that patients with Parkinson’s disease have a higher risk (2- to approximately 6-fold higher) of developing melanoma than the general population. Whether the increased risk observed was due to Parkinson’s disease or other factors, such as drugs used to treat Parkinson’s disease, is unclear. For the reasons stated above, patients and healthcare providers are advised to monitor for melanomas frequently and on a regular basis when using AA-LEVOCARB CR for any indication. Ideally, periodic skin examinations should be performed by appropriately qualified individuals (e.g., dermatologists).
7.1 Special Populations
7.1.1 Pregnant Women
Although the effects of AA-LEVOCARB CR on human pregnancy and lactation are unknown, both levodopa and combinations of carbidopa and levodopa have caused visceral and skeletal malformations in rabbits (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology). Therefore, use of AA-LEVOCARB CR in women of child-bearing potential requires that the anticipated benefits of the drug be weighed against possible hazards to the mother and to the fetus.
7.1.2 Breast-feeding
It is not known whether carbidopa is excreted in human milk. In a study of one nursing mother with Parkinson’s disease, excretion of levodopa in breast milk was reported. AA-LEVOCARB CR should not be given to nursing mothers unless the anticipated benefits to the mother outweigh the potential hazards to the infant.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness of AA-LEVOCARB CR has not been established in pediatric patients; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience with levodopa/carbidopa combinations suggest that use in the geriatric population is not associated with differences in safety or effectiveness (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most commonly reported adverse reaction was dyskinesia (12.8%). Occasionally, prolonged, and at times, severe afternoon dyskinesias have occurred in some patients. (See 7 WARNINGS AND PRECAUTIONS, Neurologic, Dyskinesia)
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In controlled clinical trials involving 748 patients with moderate to severe motor fluctuations, levodopa/carbidopa controlled-release tablets did not produce side effects which were unique to the controlled-release formulation.
Table 3 – Treatment-Emergent Adverse Events: Incidence in Controlled Clinical Trials Involving Patients with Moderate to Severe Motor Fluctuations
AA-LEVOCARB CR n = 748 (%) | |
Eye Blurred vision | 1.1 |
Gastrointestinal Nausea Dry mouth Constipation Vomiting Diarrhea | 5.5 2.3 1.5 1.3 1.2 |
General Asthenia Chest pain | 2.0 1.7 |
Injury, poisoning and procedural complications Falling | 1.6 |
Metabolism and nutrition Anorexia | 1.9 |
Nervous System Dyskinesia Dizziness Headache Chorea Somnolence* Dream abnormalities Dystonia Insomnia On-off phenomenon | 12.8 3.5 2.5 2.5 2.1 2.1 2.0 1.7 1.2 |
AA-LEVOCARB CR n = 748 (%) | |
Psychiatric Hallucinations Confusion Depression | 5.3 4.9 2.5 |
Respiratory, thoracic and mediastinal Dyspnea | 1.6 |
*Including very rarely excessive daytime somnolence and sudden sleep onset episodes
8.3 Less Common Clinical Trial Adverse Reactions
Adverse reactions occurring infrequently (less than 1%) were:
Cardiac disorders: Palpitation (0.8%).
Gastrointestinal disorders: Gastrointestinal pain (0.9%), dyspepsia (0.8%).
General disorders and administration site conditions: Fatigue (0.9%).
Investigations: Weight loss (0.8%).
Musculoskeletal and connective tissue disorders: Muscle cramps (0.9%).
Nervous system disorders: Paresthesia (0.9%), disorientation (0.8%), decreased mental acuity (0.7%), extrapyramidal disorder (0.7%), gait abnormalities (0.7%), agitation (0.5%), memory impairment (0.5%).
Psychiatric disorders: Anxiety disorder (0.8%).
Vascular disorders: Orthostatic hypotension (0.8%), Hypotension (0.5%).
Other adverse reactions reported in clinical trials or in post-marketing experience include (see also 8.5 Post-Market Adverse Reactions):
Cardiac disorders: Cardiac irregularities, myocardial infarction, syncope.
Eye disorders: Blurred vision.
Gastrointestinal disorders: Dark saliva, dysphagia, heartburn, taste alterations.
Musculoskeletal and connective tissue disorders: Back pain, leg pain, shoulder pain.
Nervous system disorders: Increased tremor, neuroleptic malignant syndrome (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Neuroleptic Malignant Syndrome), peripheral neuropathy.
Psychiatric disorders: Nervousness, sleep disorders, psychotic episodes including delusions and paranoid ideation.
Renal and urinary disorders: Dark urine, urinary incontinence, urinary frequency, urinary tract infection.
Respiratory, thoracic and mediastinal disorders: Cough, common cold, pharyngeal pain, upper respiratory infection.
Skin and subcutaneous tissue disorders: Angioedema, urticaria, pruritus, bullous lesions (including pemphigus-like reactions), flushing, alopecia, rash, dark sweat, malignant melanoma (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Skin).
Vascular disorders: Orthostatic effects, hypertension, hypotensive episodes.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Laboratory tests which have been reported to be abnormal are alkaline phosphatase, SGOT (AST), SGPT (ALT), lactic dehydrogenase, bilirubin, blood urea nitrogen, creatinine, uric acid, and Coomb's test.
Decreased hemoglobin and hematocrit, elevated serum glucose, and white blood cells bacteria and blood in the urine have been reported.
Decreased white blood cell count and serum potassium; protein and glucose in urine have been reported with levodopa alone and with various levodopa-carbidopa formulations, and may occur with AA-LEVOCARB CR.
8.5 Post-Market Adverse Reactions
In post-marketing use, pathological (compulsive) gambling, increased libido, hypersexuality, compulsive spending/buying, and binge/compulsive eating have been reported with dopamine agonists and/or other dopaminergic treatments, and rarely in patients treated with levodopa, including levodopa/carbidopa controlled-release tablets (see 7 WARNINGS AND PRECAUTIONS, Psychiatric).
Other adverse reactions that have been reported with levodopa or levodopa/carbidopa immediate-release tablets and may be potential side effects with AA-LEVOCARB CR are listed below.
Blood and lymphatic system disorders: Leukopenia, hemolytic and non-hemolytic anemia, thrombocytopenia, agranulocytosis.
Cardiac disorders: Arrhythmias.
Eye disorders: Diplopia, dilated pupils, oculogyric crisis.
Gastrointestinal disorders: Sialorrhea, bruxism, hiccups, gastrointestinal bleeding, flatulence, burning sensation of tongue, development of duodenal ulcer.
General disorders and administration site conditions: Edema, malaise, hot flashes.
Immune system disorders: Henoch-Schonlein purpura.
Investigations: Non-specific ECG changes, weight gain.
Nervous system disorders: Ataxia, numbness, increased hand tremor, muscle twitching, blepharospasm (which may be taken as an early sign of excess dosage, consideration of dosage reduction may be needed at this time), trismus, activation of latent Horner's syndrome, bradykinetic episodes, faintness, sense of stimulation.
Convulsions have occurred; however, a causal relationship with levodopa or levodopa/carbidopa combinations has not been established.
Psychiatric disorders: Euphoria and dementia, depression with suicidal tendencies.
Renal and urinary disorders: Urinary retention, hematuria.
Reproductive system and breast disorders: Priapism.
Respiratory, thoracic and mediastinal disorders: Hoarseness, bizarre breathing patterns.
Skin and subcutaneous tissue disorders: Increased sweating, pruritus.
Vascular disorders: Phlebitis.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Caution is advised when AA-LEVOCARB CR is used with other concomitant medications to avoid drug interactions (see 9.4 Drug-Drug Interactions).
9.3 Drug-Behavioural Interactions
See 7 WARNINGS AND PRECAUTIONS, Psychiatric, Behavioural Changes.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Anesthetics | T | When general anesthesia is required, AA-LEVOCARB CR should be discontinued the night before. Therapy with AA-LEVOCARB CR may be continued as soon as the patient is able to take medication by mouth. | |
| Antihypertensive Drugs | T | Symptomatic postural hypotension has occurred when levodopa/ decarboxylase inhibitor combinations were added to the treatment of patients receiving anti-hypertensive drugs. | When therapy with AA-LEVOCARB CR is started, dosage adjustment of the antihypertensive drug may be required. Caution should be exercised when antihypertensive drugs are administered concomitantly with AA-LEVOCARB CR. |
Dopamine Depleting Agents (e.g., reserpine1, tetrabenazine, or other drugs known to deplete monoamine stores) | T | Reduction in patient response to levodopa may occur. | Concomitant use with AA-LEVOCARB CR is not recommended. Caution should be exercised when dopamine depleting agents are administered concomitantly with AA-LEVOCARB CR. |
| Iron | C | Studies have demonstrated that ferrous sulphate decreases the bioavailability of carbidopa and/or levodopa. Because this interaction may be due to the formation of drug-iron complexes, other iron supplement formulations and iron-containing multivitamins may have similar effects. | Caution should be exercised when iron supplements are administered concomitantly with AA-LEVOCARB CR. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Isoniazid | T | Isoniazid may reduce the therapeutic effects of levodopa. | Caution should be exercised when isoniazid is administered concomitantly with AA-LEVOCARB CR. |
| Metoclopramide | T | Although metoclopramide may increase the bioavailability of levodopa by increasing gastric emptying, metoclopramide may also adversely affect disease control by its dopamine receptor antagonistic properties. | Caution should be exercised when metoclopramide is administered concomitantly with AA-LEVOCARB CR. |
| Dopamine D2 receptor antagonists (e.g., phenothiazines, butyrophenones and risperidone) | T | May reduce the therapeutic effects of levodopa. The beneficial effects of levodopa in Parkinson's disease have been reported to be reversed by phenytoin and papaverine. | Patients taking these drugs with AA-LEVOCARB CR should be observed carefully for loss of therapeutic response. |
| Selegiline | T | Concomitant therapy with selegiline and levodopa/carbidopa preparations may be associated with severe orthostatic hypotension not attributable to levodopa/carbidopa alone (see 2 CONTRAINDICATIONS). | AA-LEVOCARB CR may be administered concomitantly with a MAO inhibitor with selectivity for MAO type B (e.g. selegiline HCl) (see 2 CONTRAINDICATIONS) at the manufacturer’s recommended dose which maintains selectivity for MAO type B. |
| Tricyclic antidepressants | T | There have been rare reports of adverse reactions, including hypertension and dyskinesia, resulting from the concomitant use of tricyclic antidepressants and levodopa/carbidopa preparations. | For patients receiving monoamine oxidase inhibitors, see 2 CONTRAINDICATIONS; 9.1 Serious Drug Interactions. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Since levodopa competes with certain amino acids, the absorption of levodopa may be impaired in some patients on a high protein diet.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
AA-LEVOCARB CR may cause a false-positive reaction for urinary ketone bodies when a tape test is used for determination of ketonuria. This reaction will not be altered by boiling the urine specimen. False-negative tests may result with the use of glucose-oxidase methods of testing for glucosuria.
Cases of falsely diagnosed pheochromocytoma in patients with levodopa-carbidopa therapy have been reported very rarely. Caution should be exercised when interpreting the plasma and urine levels of catecholamines and their metabolites in patients on levodopa or levodopa-carbidopa therapy.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The symptoms of Parkinson's disease are related to depletion of dopamine in the corpus striatum. While the administration of dopamine is ineffective in the treatment of Parkinson's disease because it does not cross the blood-brain barrier, levodopa, the metabolic precursor of dopamine, does cross the blood-brain barrier and is converted to dopamine in the basal ganglia. This is thought to be the mechanism whereby levodopa relieves the symptoms of Parkinson's disease.
Carbidopa, a decarboxylase inhibitor, does not cross the blood-brain barrier and does not affect the metabolism of levodopa within the central nervous system. Since its decarboxylase inhibiting activity is limited to peripheral tissues, administration of carbidopa with levodopa makes more levodopa available for transport to the brain. Combined therapy with levodopa and carbidopa reduces the amount of levodopa required for optimum therapeutic benefit by about 75 to 80%, permits an earlier response to therapy, and also reduces the incidence of nausea, vomiting and cardiac arrhythmias. Combined therapy, however, does not decrease adverse reactions due to central effects of levodopa.
10.2 Pharmacodynamics
AA-LEVOCARB CR, a combination of levodopa, the metabolic precursor of dopamine, and carbidopa, an aromatic amino acid decarboxylase inhibitor, is available in a polymer-based controlled-release tablet formulation. Levodopa/Carbidopa controlled-release tablets can be useful in reducing "off" time in patients treated previously with a conventional
levodopa/decarboxylase inhibitor combination who have had predictable peak dose dyskinesias and unpredictable motor fluctuations.
Levodopa is rapidly decarboxylated to dopamine in peripheral tissues so that only a small portion of a given dose is transported unchanged to the central nervous system. For this reason, large doses of levodopa are required for adequate therapeutic effect and these may often be attended by nausea and other adverse reactions, some of which are attributable to dopamine formed in peripheral tissues.
Following years of treatment with preparations containing levodopa, an increasing number of parkinsonian patients develop fluctuations in motor performance and dyskinesias. The advanced form of motor fluctuations ('on-off' phenomenon) is characterized by unpredictable swings from mobility to immobility. Although the causes of the motor fluctuations are not completely understood, it has been demonstrated that they can be attenuated by treatment regimens that produce steady plasma levels of levodopa.
In clinical trials, patients with motor fluctuations experienced reduced "off" time with levodopa/ carbidopa controlled-release tablets when compared with levodopa/carbidopa immediate-release tablets. Global ratings of improvement and activities of daily living in the "on" and "off" states, as assessed by both patient and physician, were slightly better in some patients during therapy with levodopa/carbidopa controlled-release tablets than with levodopa/carbidopa immediate-release tablets. In patients without motor fluctuations, levodopa/carbidopa controlled-release tablets provided therapeutic benefit similar to levodopa/carbidopa immediate-release tablets, but with less frequent dosing.
Pyridoxine hydrochloride (vitamin B6), in oral doses of 10 mg to 25 mg, may reverse the effects of levodopa by increasing the rate of aromatic amino acid decarboxylation. Carbidopa inhibits this action of pyridoxine.
Levodopa: Pharmacological experiments in various species of animals have shown that levodopa produced increased motor activity, aggressive behaviour and electroencephalographic alerting behaviour. However, occasional sedation and ataxia have also been reported in some animal species. Levodopa also reverses the reserpine induced Parkinson-like effects in animals. Cardiovascular studies in dogs and cats have shown that levodopa increases the catecholamine levels in the brain which has been evident in an initial increase in blood pressure followed by a secondary decrease in blood pressure. The changes in blood pressure appear to correlate with the changes in renal function.
Carbidopa: In the absence of biogenic amine precursors, carbidopa is singularly inert pharmacologically. Carbidopa lacks effects upon blood pressure in normal, neurogenic hypertensive, or renal hypertensive dogs. It also does not affect heart rate, exhibit ganglionic, adrenergic, or peripheral anticholinergic properties, or influence renal electrolyte excretion in this species. In mice or rats, carbidopa does not appreciably affect gastric secretion, nor gastric or colonic motility. The compound does not antagonize electroshock or pentylenetetrazol-induced convulsions in mice; neither does it exhibit analgesic activity or affect fixed interval-fixed ratio reinforcement behaviour in rats. Overt behavioural effects have not been observed with carbidopa in the rhesus monkey, dog, rat, mouse or pigeon. The dose levels of carbidopa used in the latter investigations were in excess of those necessary to inhibit aromatic amino acid decarboxylase or to alter the actions of levodopa. The studies suggest that carbidopa, when administered alone at dose levels effective in inhibiting aromatic amino acid decarboxylases, lacks appreciable effects upon the cardiovascular, gastrointestinal, renal or central nervous systems.
Levodopa and Carbidopa Combination: Levodopa increases motor activity and irritability, and antagonizes reserpine-induced hypothermia, suppressed locomotion, and ptosis in mice. All these effects are enhanced two- to six-fold by pre-treatment with carbidopa. Increased motor activity induced by levodopa in rats also is enhanced by pre-treatment with carbidopa. In contrast, levodopa-induced vomiting is decreased significantly in dogs and pigeons by pre-treatment with carbidopa.
10.3 Pharmacokinetics
Absorption
AA-LEVOCARB CR 200 mg/50 mg: Levodopa/carbidopa controlled-release tablets 200 mg/50 mg contain levodopa, 200 mg, and carbidopa, 50 mg, per tablet in controlled-release formulation, designed to release the active ingredients over a 4- to 6-hour period.
The absorption of levodopa following levodopa/ carbidopa controlled-release tablets, 200 mg/50 mg, is gradual and continuous for 4 to 5 hours, although the majority of the dose is absorbed in 2 to 3 hours. With conventional levodopa/carbidopa immediate-release tablets, absorption is rapid and is virtually complete in 2 to 3 hours. The pharmacokinetic parameters of levodopa, following the administration of levodopa/carbidopa controlled-release tablets, 200 mg/50 mg, and conventional levodopa/carbidopa immediate-release tablets to healthy, elderly volunteers, are presented in the following table:
Table 5 - Summary of Pharmacokinetic Parameters of Levodopa in Healthy Elderly Volunteers.
| Single Dose | Steady State | |||||||||||||
Immediate-Release 2 x 100 mg/25 mg | Controlled-Release 200 mg/50 mg | Immediate-Release 2 x 100 mg/25 mg | Controlled-Release 200 mg/50 mg | |||||||||||
| Bioavailability* (%) | -- | -- | 99 | 71 | ||||||||||
| Cmax (mcg/mL) | 3.26 | 1.15 | 3.20 | 1.14 | ||||||||||
Trough Cp at 8 hr (mcg/mL) | 0.048 | 0.090 | 0.074 | 0.163 | ||||||||||
| Peak time (hr) | 0.5 | 2.1 | 0.7 | 2.4 | ||||||||||
| AUC (mcg•hr/mL) | 5.31 | 4.01 | 5.62 | 4.19 | ||||||||||
*Relative to an intravenous dose
In general, peak levodopa plasma levels are lower, bioavailability is less and time to reach peak levels is delayed when using levodopa/carbidopa controlled-release tablets. Levodopa plasma levels following a single dose are essentially identical to those following repeated administration. However, with levodopa/carbidopa controlled-release tablets, levodopa plasma concentrations fluctuate less, namely peak plasma levels are lower and end of dose levels (trough concentrations) higher than after conventional therapy.
The bioavailability of 2 half tablets of levodopa/carbidopa controlled-release formulation, 200 mg/ 50 mg, is approximately 20% greater than that of one intact tablet. The bioavailability of levodopa/carbidopa controlled-release tablets is somewhat increased in the presence of food. Dose-proportionality has been demonstrated over the dose range of one and two levodopa/ carbidopa controlled-release tablets, 200 mg/50 mg.
AA-LEVOCARB CR 100 mg/25 mg: The pharmacokinetics of levodopa following administration of levodopa/carbidopa controlled-release tablets, 100 mg/25 mg were studied in patients with Parkinson's disease. Chronic three month, open-label, twice daily dosing with levodopa/carbidopa controlled-release tablets, 100 mg/25 mg (range: 200 mg levodopa, 50 mg carbidopa up to 600 mg levodopa, 150 mg carbidopa per day) did not result in accumulation of plasma levodopa. The dose-adjusted bioavailability for one levodopa/carbidopa controlled-release tablet, 100 mg/25 mg, was equivalent to that for one levodopa/carbidopa controlled-release tablet, 200 mg/50 mg. The mean peak concentration of levodopa following the administration of one levodopa/carbidopa controlled-release tablet, 100 mg/25 mg, was greater than 50% of that following the administration of one levodopa/carbidopa controlled release tablet, 200 mg/50 mg. Mean time-to-peak plasma levels may be slightly less for levodopa/carbidopa controlled-release tablets, 100 mg/25 mg, than for levodopa/ carbidopa controlled-release tablets, 200 mg/50 mg.
Distribution
Levodopa and Carbidopa Combination: Decarboxylation within peripheral organs and the walls of the brain capillaries limits the portion of an administered dose of levodopa accessible to most central nervous structures. Inhibition of peripheral aromatic amino acid decarboxylase enhances the accumulation of levodopa in the blood and increases the amount of this amino acid available to the brain. If brain decarboxylase is not also inhibited, the result is a marked accumulation of dopamine in the brain. Such a mechanism explains the marked enhancement of brain dopa and dopamine levels which results when levodopa is administered in combination with carbidopa which does not penetrate central nervous system structures even when administered in high doses.
Tissue distribution of radioactivity in rats, sacrificed one hour after an intravenous dose of 20 mg/kg of 14C-carbidopa, showed the major portion of radioactivity to be concentrated in the kidneys, lungs, small intestine, and liver; in descending order. None was detected in the brain.
Metabolism
Levodopa: Biochemical studies in vivo as well as in vitro have demonstrated that levodopa is decarboxylated to dopamine in many tissues. Levodopa crosses the blood-brain barrier and elevates the dopamine concentration in the brain. The dopamine formed can be degraded to dihydroxyphenylacetic and homovanillic acids which are the two major metabolites in the urine. Dopamine may also be converted to noradrenaline, in which case the major metabolites are vanillylmandelic acid and dihydroxy-mandelic acid.
Elimination
Elimination half-life of levodopa in the presence of carbidopa is about 1.5 hours. Following AA-LEVOCARB CR, the apparent half-life of levodopa may be prolonged because of continuous absorption.
Following an oral dose of radioactive labelled carbidopa to healthy subjects and to patients with Parkinson's disease, maximal plasma levels of radioactivity were reached in two to four hours in the healthy subjects and in one and one-half to five hours in the patients. Approximately equal quantities were excreted in the urine and the feces by both groups. Comparison of urinary metabolites in healthy subjects and patients indicated that the drug is metabolized to the same degree in both. Urinary excretion of unchanged drug was essentially complete in seven hours and represented 35 percent of the total urinary radioactivity. Only metabolites were present thereafter.
In monkeys, an oral dose of levodopa given one hour after a dose of radioactive labelled carbidopa had no significant effect on the absorption or excretion of carbidopa. Peak plasma levels of radioactivity were achieved in the same period of time and disappeared at the same rate as with carbidopa alone.
Carbidopa is incompletely absorbed in the rat, dog and rhesus monkey. Following oral administration of a dose of 14C labelled drug, the percentages of radioactive carbon excreted in urine were16% for rat, 66% for dog and 40% for monkey; and in feces were 52% for rat, 11% for dog and 32% for monkey. Urines contained both unchanged drug and metabolites.
11 STORAGE, STABILITY AND DISPOSAL
AA-LEVOCARB CR should be stored at room temperature (15°C to 30°C). Protect from light and moisture.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Levodopa
Chemical name: 1) L-Tyrosine,3-hydroxy-
- 2) (-)-3-(3,4-Dihydroxyphenyl)-L-alanine
Molecular formula and molecular mass: C9H11NO4 and 107.19 g/mol
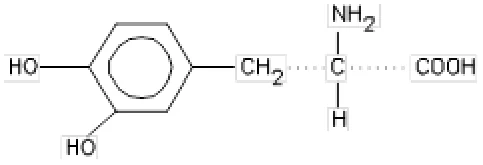
Structural formula:
Physicochemical properties: White to off white, odourless, crystalline powder. In the presence of moisture, is rapidly oxidized by atmospheric oxygen and darkens. Slightly soluble in water; freely soluble in 3N hydrochloric acid; insoluble in alcohol.
Proper name: Carbidopa
Chemical name: 1)Benzenepropanoic acid,α-hydrazino-3,4-dihydroxy-α-methyl,monohydrate,(S)
2)(-)-L-α-Hydrazino-3,4-di-hydroxy-α-methylhydrocinnamic acid monohydrate.
Molecular formula and molecular mass: C10H14N2O4.H2O and 244.25 g/mol (Tablet content is expressed in terms of anhydrous carbidopa, which has a molecular weight of 226.3 g/mol)
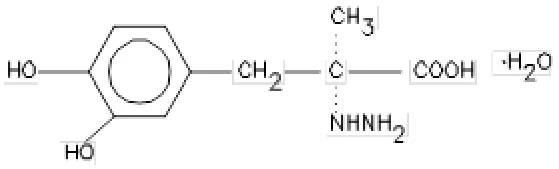
Structural formula:
Physicochemical properties: White to creamy white, odourless or practically odourless powder. Slightly soluble in water; freely soluble in 3N hydrochloric acid; slightly soluble in methanol; practically insoluble in alcohol, in acetone, in chloroform and in ether.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
The clinical trial data on which the original indication was authorized is not available for AA-LEVOCARB CR (levodopa and carbidopa controlled-release tablets).
14.2 Comparative Bioavailability Studies
Three comparative bioavailability studies were performed, one under fasted, one under fed and one under steady-state conditions. The double-blind, randomized, two-way crossover studies were conducted in healthy, adult, male volunteers to evaluate the relative bioavailability of 1 x 50 mg/ 200 mg doses of AA-LEVOCARB CR Tablet manufactured by AA Pharma Inc. and SINEMET® CR Tablet manufactured by Merck Sharp & Dohme, Canada. The mean pharmacokinetic parameters of these subjects are summarized in the following tables:
Summary of the Comparative Bioavailability Data - Fasting Study
Carbidopa (1x50 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 582.1 675.1 (50.9) | 559.3 628.6 (46.6) | 104.1 | 94-116 |
AUCI (ng•h/mL) | 602.8 693.5 (49.7) | 578.7 646.6 (45.6) | 104.2 | 94-116 |
Cmax (ng/mL) | 117.2 133.0 (45.4) | 114.2 126.4 (44.0) | 102.6 | 94-112 |
| Tmax3 (h) | 3.985 (23.6) | 3.515 (31.5) | Not applicable | Not applicable |
| T½3 (h) | 2.353 (29.7) | 2.355 (18.3) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
Summary of the Comparative Bioavailability Data - Fasting Study
Levodopa (1x200 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 3448 3599 (29.9) | 3601 3699 (23.9) | 95.75 | 90-101 |
AUCI (ng•h/mL) | 3523 3674 (29.5) | 3676 3773 (23.6) | 95.84 | 90-101 |
Cmax (ng/mL) | 816.8 851.8 (30.0) | 886.0 929.1 (32.7) | 92.19 | 86-99 |
| Tmax3 (h) | 2.561 (28.4) | 2.167 (40.2) | Not applicable | Not applicable |
| T½3 (h) | 1.577 (13.2) | 1.597 (12.5) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
Summary of the Comparative Bioavailability Data - Study with Food (High fat meal)
Carbidopa (1x50 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 440.0 476.6 (44.8) | 444.6 486.7 (44.0) | 98.97 | 91-107 |
AUCI (ng•h/mL) | 455.4 491.3 (43.6) | 459.1 500.2 (43.0) | 99.19 | 92-107 |
Cmax (ng/mL) | 91.70 99.31 (42.1) | 95.05 102.9 (41.9) | 96.48 | 89-104 |
| Tmax3 (h) | 4.791 (23.6) | 4.292 (26.2) | Not applicable | Not applicable |
| T½3 (h) | 1.931 (18.0) | 1.958 (14.1) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
Summary of the Comparative Bioavailability Data - Study with Food (High fat meal)
Levodopa (1x200 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 3524 3621 (24.9) | 3562 3679 (26.3) | 98.93 | 97-102 |
AUCI (ng•h/mL) | 3604 3699 (24.3) | 3635 3752 (25.9) | 99.15 | 97-102 |
Cmax (ng/mL) | 938.1 992.7 (35.5) | 1106 1152 (29.0) | 84.82 | 79-92 |
| Tmax3 (h) | 3.629 (25.4) | 3.052 (28.2) | Not applicable | Not applicable |
| T½3 (h) | 1.531 (11.6) | 1.540 (11.6) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
Summary of the Comparative Bioavailability Data - Steady-State Study
Carbidopa (1x50 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCτ (ng•h/mL) | 598.3 648.95 (42.2) | 630.3 687.37 (44.5) | 94.92 | 82-109 |
Cmax (ng/mL) | 128.2 140.07 (45.2) | 145.9 164.65 (50.7) | 87.87 | 74-104 |
Cmin (ng/mL) | 23.85 27.96 (61.3) | 23.76 27.65 (59.8) | 100.38 | 83-119 |
| Tmax3 (h) | 3.360 (29.3) | 3.446 (38.6) | Not applicable | Not applicable |
| FL3 (%) | 140.4 (29.7) | 159.6 (39.1) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
Summary of the Comparative Bioavailability Data - Steady-State Study
Levodopa (1x200 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCτ (ng•h/mL) | 4028 4156.36 (25.1) | 4303 4403.72 (21.5) | 93.61 | 87-100 |
Cmax (ng/mL) | 1064 1100.64 (27.9) | 1176 1225.12 (29.3) | 90.48 | 83-99 |
Cmin (ng/mL) | 94.65 108.96 (51.8) | 89.56 100.67 (48.6) | 105.68 | 90-123 |
| Tmax3 (h) | 2.082 (31.4) | 1.564 (61.9) | Not applicable | Not applicable |
| FL3 (%) | 193.6 (19.2) | 204.3 (22.0) | Not applicable | Not applicable |
1 AA-LEVOCARB CR (levodopa and carbidopa), 200 mg / 50 mg tablets, AA Pharma Inc.
2 SINEMET CR (levodopa and carbidopa), 200 mg / 50 mg tablets, Merck Sharp & Dohme, Canada
3 Expressed as the arithmetic mean (CV%) only.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Toxicity: The following table summarizes the acute toxicity data for levodopa and carbidopa alone and in combination. Mortality usually occurred in 12 hours with carbidopa and 30 minutes with levodopa. With the combination of levodopa and carbidopa, deaths occurred between 30 minutes and 24 hours at high doses and up to 12 days with lower doses. The toxicity did not continue to decrease with drug ratios above 1:3.
Table 6 - Summary of Acute Oral Toxicity Data
| Species | Sex | LD50 (mg/kg) | Signs of Toxicity |
| A) CARBIDOPA | |||
Rat (A&W) Rat (A&W) Rat (I) Mouse (A) | F M M & F F | 4810 5610 2251 1750 | Ptosis, ataxia, decreased activity. As above plus bradypnea. |
| B) LEVODOPA | |||
| Species | Sex | LD50 (mg/kg) | Signs of Toxicity |
Rat (A) Rat (A) Mouse | F M F | 2260 1780 1460 | Vocalization, irritability, excitability, increased activity followed by decreased activity. |
| C) LEVODOPA/CARBIDOPA (1:1) | |||
| Mouse | M & F | 1930* | Erect tail, piloerection, ataxia, lacrimation, increased activity & irritability, clonic convulsion. |
| D) LEVODOPA/CARBIDOPA (3:1) | |||
| Mouse | M & F | 3270* | As above. |
*Sum of individual doses of levodopa/carbidopa A - Adult; W - Weanling; I - Infant
Acute oral interaction studies in mice demonstrated that pre-treatment with pharmacological doses (1 mg/kg) of benztropine mesylate or trihexyphenidyl hydrochloride did not affect the acute toxicity of carbidopa, levodopa or a 1:3 mixture of carbidopa: levodopa.
Higher doses (24 to 184 mg/kg) increased the acute toxicity of carbidopa and the combination but not of levodopa. Pre-treatment with a MAO inhibitor (phenelzine) resulted in a five-fold increase in acute toxicity of the mixture and a four-fold increase in toxicity of levodopa with no change in toxicity of carbidopa. Synergism between a 10:1 mixture of levodopa:carbidopa and amantadine was indicated by increased toxicity in the female mouse. However, no synergism was demonstrated between therapeutic doses of amantadine and carbidopa, levodopa or a 1:10 mixture.
Subacute Toxicity: In oral subacute toxicity studies, carbidopa is more toxic for dogs than for monkeys or rats. Following doses of 45 mg/kg/day for six weeks, dogs exhibited anorexia, emesis, tarry stools, diarrhea, dry nose and/or gums, fine muscular tremors, weight loss, prolonged clotting and prothrombin times, bilirubinuria and decreases in total leukocytes, total protein and albumin, and SGOT activity. The increased toxicity in dogs appeared to be due to pyridoxine-deficiency, since concurrent administration of pyridoxine decreased the toxicity of carbidopa. Doses up to 135 mg/kg/day produced no drug-related effects in the monkey and only flaccidity in some rats. Slight centrolobular vacuolization of hepatocytes in two rats and significantly higher mean kidney weights were observed in the highest dosage group.
Subchronic Toxicity: Oral toxicity studies with doses of levodopa up to 1000 mg/kg/day for 13 weeks indicated no treatment-related effects in monkeys. In rats, treatment-related morphologic changes occurred in salivary glands (hypertrophy of acinar cells) and adrenals (cytoplasmic rarefaction of the zona glomerulosa) at all dosage levels, in kidneys of rats receiving 500 and 1000 mg/kg/day (tubular necrosis with regeneration and necrosis respectively) and in the stomach (focal necrosis of the superficial epithelium) of some rats in the high dosage group. A statistically significant leukocytosis and increase in heart and kidney weights occurred in females of this latter group; males had a significant increase in heart and liver weights and a decrease in growth rate. Clinical signs of toxicity included ptyalism, piloerection, hyperventilation with intermittent dyspnea and decreased activity.
Combinations of levodopa and carbidopa in respective doses of 30/30, 30/60 and
30/120 mg/kg/day were given orally for 14 weeks to monkeys and for 13 weeks to rats. Signs of toxicity in monkeys were related to dosage and indicated that coadministration enhanced the pharmacologic activity of levodopa. In the rat, the apparent degree of potentiation of levodopa by carbidopa appeared to be less.
Chronic Toxicity: Three dosage ratios of levodopa and carbidopa were given orally to monkeys and rats for 54 weeks. Dosages of 10/20 mg/kg/day had no apparent physical effects while hyperactivity occurred in monkeys at dosages of 10/50 and 10/100 mg/kg/day and continued for 32 weeks with the higher dose. Muscular incoordination and weakness were observed until the twenty-second week with the 10/100 mg/kg/day dose. Pathologic studies did not show any morphologic changes. Rats that received 10/50 and 10/100 mg/kg/day had a decrease in normal activity and displayed abnormal body positions. The higher dose caused excessive salivation. There was a decrease in body weight gain. Morphological changes, where present, were those noted with levodopa alone.
Reproductive and Developmental Toxicology
The incidences of malformations of the heart and great vessels were 0 of 105, 1 of 94, and 6 of 81 fetuses from rabbits given 75, 125 or 250 mg of levodopa/kg/day respectively by the oral route, indicating a dose-dependent teratogenic effect. Anomalies included septal defects, constricted or missing ductus arteriosus, enlarged aortic arches, fused aortas and pulmonary arches, and transpositions. The same types of malformations were also induced in fetuses from rabbits given doses of various combinations of levodopa and carbidopa, but they were not observed when carbidopa was given alone. The malformations, possibly drug-related, were also seen in one mouse fetus from a dam which had received 500 mg of levodopa/kg/day. No drug-induced malformations were observed in fetuses of mice given various combinations of the two drugs or in the offspring of rats given carbidopa. The significance of heart and great vessel malformations in one stunted fetus from a female mouse given the lowest dose of carbidopa (30 mg/kg/day) and in one stillborn pup from a female rat given the mid-dose of the drug combination (10 mg) of carbidopa/kg plus 50 mg of levodopa/kg/day is questionable; both offspring also had other external, cranial and skeletal malformations.
Other effects on reproduction associated with combination treatments in the rabbit included decreased maternal weight gains and fetal weights, and increased resorptions, and incidences of various skeletal anomalies, especially of vertebral centra and skull bones. In mice given the combination product, only a decrease in fetal weight occurred. In rats, none of these effects were observed; the maximal dose administered was 10 mg of carbidopa/kg plus 100 mg of levodopa/kg/day.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1 SINEMET® CR (levodopa and carbidopa controlled-release tablets), submission control: 169999, Product Monograph, Merck Canada Inc. (FEB 06, 2014)