


Product Monograph - Act Ezetimibe
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | tablet 10 mg | Lactose monohydrate, croscarmellose sodium, hypromellose, sodium lauryl sulfate, crospovidone, microcrystalline cellulose and magnesium stearate. |
INDICATIONS AND CLINICAL USE
ACT EZETIMIBE (ezetimibe) is indicated as an adjunct to lifestyle changes, including diet, when the response to diet and other non-pharmacological measures alone has been inadequate.
Primary Hypercholesterolemia
ACT EZETIMIBE, administered alone or with an HMG-CoA reductase inhibitor (statin), is indicated for the reduction of elevated total cholesterol (total-C), low density lipoprotein cholesterol (LDL-C), apolipoprotein B (Apo B), and triglycerides (TG) and to increase high density lipoprotein cholesterol (HDL-C) in patients with primary (heterozygous familial and non-familial) hypercholesterolemia.
Homozygous Familial Hypercholesterolemia (HoFH)
ACT EZETIMIBE, administered with a statin, is indicated for the reduction of elevated total-C and LDL-C levels in patients with HoFH as an adjunct to treatments such as LDL apheresis or if such treatments are not possible.
Homozygous Sitosterolemia (Phytosterolemia)
ACT EZETIMIBE is indicated for the reduction of elevated sitosterol and campesterol levels in patients with homozygous familial sitosterolemia.
CONTRAINDICATIONS
Hypersensitivity to any component of this medication.
When ACT EZETIMIBE is to be administered with a statin, the contraindications to that medication should be reviewed before starting concomitant therapy.
The combination of ACT EZETIMIBE with a statin is contraindicated in patients with active liver disease or unexplained persistent elevations in serum transaminases.
All statins are contraindicated in pregnant and nursing women. When ACT EZETIMIBE is administered with a statin in a woman of childbearing potential, refer to the product labeling for that medication (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
When ACT EZETIMIBE is to be administered with a statin, please refer also to the Product Monograph for that medication. Note that all statins are contraindicated in pregnant women (see the Product Monograph for the medication; see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women).
Hepatic/Biliary/Pancreatic
Concomitant Administration with a Statin: When ACT EZETIMIBE is initiated in a patient already taking a statin, liver function tests should be considered at initiation of ACT EZETIMIBE therapy, and then as indicated (see ADVERSE REACTIONS, Abnormal Hematologic and Clinical Chemistry Findings).
When ACT EZETIMIBE is initiated at the same time as a statin, liver function tests should be performed at initiation of therapy and according to the recommendations of that medication (see ADVERSE REACTIONS, Abnormal Hematologic and Clinical Chemistry Findings).
Liver Enzymes: In controlled monotherapy studies, the incidence of consecutive elevations (≥ 3 times the upper limit of normal [ULN]) in serum transaminases was similar between ezetimibe (0.5%) and placebo (0.3%).
In controlled co-administration trials in patients receiving ezetimibe with a statin, the incidence of consecutive transaminase elevations (≥ 3 X ULN) was 1.3% compared to 0.4% in patients on a statin alone.
Patients with Liver Impairment: The pharmacokinetics of ezetimibe were examined in patients with impaired liver function as defined by the Child-Pugh scoring system.
- In patients with mild hepatic insufficiency (Child-Pugh score 5 or 6), the mean area under the curve (AUC) for total ezetimibe (after a single 10 mg dose of ezetimibe was increased approximately 1.7-fold compared to healthy subjects. No dosage adjustment is necessary for patients with mild hepatic insufficiency.
- In patients with moderate hepatic insufficiency (Child-Pugh score 7 to 9), the mean AUC for total ezetimibe (after multiple doses of 10 mg daily) was increased approximately 4-fold on Day 1 and Day 14 compared to healthy subjects. Due to the unknown effects of the increased exposure to ezetimibe in patients with moderate (Child-Pugh score 7 to 9) or severe (Child-Pugh score >9) hepatic insufficiency, ezetimibe is not recommended in these patients.
- No pharmacokinetic studies with ezetimibe have been carried out in patients with either active liver disease or unexplained and persistent elevations in serum transaminases. It is recommended that care be exercised in such patients.
The co-administration of ACT EZETIMIBE and a statin is contraindicated in patients with active liver disease or unexplained and persistent elevations in serum transaminases.
Post-marketing reports of adverse events have included rare cases of hepatitis in patients taking ezetimibe, although causality has not been proven. If patients develop signs or symptoms of hepatitis, liver function should be evaluated.
Pancreatitis: Post-marketing reports of adverse events have included rare cases of acute pancreatitis occurring in patients taking ezetimibe, although causality has not been proven. The diagnosis of acute pancreatitis should be considered in patients taking ezetimibe who develop sudden acute abdominal pain.
Muscle Effects
Myopathy/Rhabdomyolysis: Myopathy and rhabdomyolysis are known adverse effects of statins. Post-marketing reports of adverse events have included rare cases of myopathy/ rhabdomyolysis occurring in patients taking ezetimibe with or without a statin, regardless of causality. Myopathy/Rhabdomyolysis should be considered in patients presenting with muscle pain during treatment with ezetimibe with or without a statin, and consideration given to discontinuation of the drugs. Most cases of myopathy/rhabdomyolysis resolved when drugs were discontinued.
Myalgia: In controlled clinical trials, the incidence of myalgia was 5.0% for ezetimibe vs 4.6% for placebo (see ADVERSE REACTIONS, Table 2). Post-marketing reports of adverse events have included myalgia in patients taking ezetimibe with or without a statin, regardless of causality. Patients should be instructed to contact their physician if they experience persistent and severe muscle pains with no obvious cause.
A number of patients treated with ezetimibe, in whom myalgia occurred had previously experienced myalgia (with or without elevated CK levels) with statin therapy. Patients with a history of statin intolerance (myalgia with or without elevated CK levels) should be closely monitored for adverse muscle events during treatment with ACT EZETIMIBE.
Renal
Renal Insufficiency: After a single 10 mg dose of ezetimibe in patients with severe renal disease, the mean AUC for total ezetimibe was increased approximately 1.5-fold, compared to healthy subjects. Accordingly, no dosage adjustment is necessary for renal impaired patients.
Special Populations
Pregnant Women
No clinical data on exposed pregnancies are available for ezetimibe. The effects of ezetimibe on labour and delivery in pregnant women are unknown. Note that all statins are contraindicated in pregnant women (see the Product Monograph for the medication). Caution should be exercised when prescribing to pregnant women.
Nursing Women
Studies in rats have shown that ezetimibe is excreted in milk. It is not known whether ezetimibe is excreted into human breast milk, therefore, ezetimibe should not be used in nursing mothers unless the potential benefit justifies the potential risk to the infant. Note that all statins are contraindicated in nursing women (see the Product Monograph for the medication).
Pediatrics
The pharmacokinetics of ezetimibe in adolescents (10 to 18 years) have been shown to be similar to that in adults. Treatment experience with ezetimibe in the pediatric population is limited to 4 patients (9 to 17 years) in the sitosterolemia study and 5 patients (11 to 17 years) in the HoFH study. Treatment with ezetimibe in children (<10 years) is not recommended.
Geriatrics
Plasma concentrations for total ezetimibe are about 2-fold higher in the elderly (≥ 65 years) than in the young (18 to 45 years). LDL-C reduction and safety profile are comparable between elderly and young subjects treated with ezetimibe. Therefore, no dosage adjustment is necessary in the elderly.
Sex
Plasma concentrations for total ezetimibe are slightly higher (<20%) in women than in men. LDL-C reduction and safety profile are comparable between men and women treated with ezetimibe. Therefore, no dosage adjustment is necessary on the basis of sex.
Race
Based on a meta-analysis of pharmacokinetic studies, there were no pharmacokinetic differences between Blacks and Caucasians.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most commonly reported adverse events in clinical studies were upper respiratory tract infection, headache, myalgia and back pain. In post-marketing use, serious adverse events reported rarely or very rarely, regardless of causality, included hepatitis, hypersensitivity reactions, pancreatitis and myopathy/rhabdomyolysis.
When ezetimibe is to be administered with a statin, please refer also to the Product Monograph for that medication.
Clinical Trial Adverse Drug Reactions
Ezetimibe clinical trial experience involved 2486 patients in placebo-controlled monotherapy trials (1691 treated with ezetimibe) and 4547 patients in active controlled trials (449 of whom were treated with ezetimibe alone and 1708 treated with ezetimibe plus a statin). The studies were of 8 to 14 weeks duration. The overall incidence of adverse events reported with ezetimibe was similar to that reported with placebo and the discontinuation rates due to treatment related adverse events was similar between ezetimibe (2.3%) and placebo (2.1%).
Monotherapy
Adverse experiences reported in ≥ 2% of patients treated with ezetimibe and at an incidence greater than placebo in placebo-controlled studies of ezetimibe, regardless of causality assessment, are shown in Table 1.
| Table 1* - Clinical Adverse Events Occurring in ≥ 2% of Patients Treated with ezetimibe and at an Incidence Greater than Placebo, Regardless of Causality | ||||
|---|---|---|---|---|
Body System/Organ Class Adverse Event | Placebo (%) N=795 | Ezetimibe (%) n=1691 | ||
Body as a whole - general disorders Fatigue | 1.8 | 2.2 | ||
Gastrointestinal system disorders Abdominal pain Diarrhea | 2.8 3.0 | 3.0 3.7 | ||
Infection and infestations Infection viral Pharyngitis Sinusitis | 1.8 2.1 2.8 | 2.2 2.3 3.6 | ||
Musculoskeletal system disorders Arthralgia Back pain | 3.4 3.9 | 3.8 4.1 | ||
Respiratory system disorders Coughing | 2.1 | 2.3 | ||
| * Includes patients who received placebo or ezetimibe alone reported in Table 2. | ||||
The frequency of less common adverse events was comparable between ezetimibe and placebo.
Only two patients out of the 1691 patients treated with ezetimibe alone reported serious adverse reactions-one with abdominal pain plus panniculitis, and one with arm pain and palpitation.
In monotherapy placebo-controlled clinical trials, 4% of patients treated with ezetimibe and 3.8% of patients treated with placebo were withdrawn from therapy due to adverse events.
The following additional drug-related adverse experiences were reported in patients taking ezetimibe alone (n = 2396) and at a greater incidence than placebo (n=1159).
Common (incidence ≥1% and <10%)
Gastrointestinal Disorders: flatulence
Uncommon (incidence ≥0.1% and <1%)
Investigations: ALT and/or AST increased; blood CPK increased; gammaglutamyltransferase increased; liver function test abnormal
Gastrointestinal Disorders: dyspepsia; gastroesophageal reflux disease; nausea
General Disorders: chest pain; pain
Musculoskeletal and Connective Tissue Disorders: muscle spasms; neck pain
Metabolism and Nutrition Disorders: decreased appetite
Vascular Disorders: hot flush; hypertension
Combination with a Statin
Ezetimibe has been evaluated for safety in combination studies in more than 2000 patients. In general, adverse experiences were similar between ezetimibe administered with a statin and a statin alone. However, the frequency of increased transaminases was slightly higher in patients receiving ezetimibe administered with a statin than in patients treated with a statin alone (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Patients with Liver Impairment).
Clinical adverse experiences reported in ≥ 2% of patients and at an incidence greater than placebo in four placebo-controlled trials where ezetimibe was administered alone or initiated concurrently with various statins, regardless of causality assessment, are shown in Table 2.
| Table 2* - Clinical Adverse Events Occurring in ≥ 2% of Patients and at an Incidence Greater than Placebo, Regardless of Causality, in Ezetimibe /Statin Combination Studies | |||||||||
|---|---|---|---|---|---|---|---|---|---|
Body System/Organ Class Adverse Event | Placebo (%) n=259 | Ezetimibe (%) N=262 | All Statins** (%) n=936 | Ezetimibe + All Statins** (%) n=925 | |||||
| Body as a whole - general disorders | |||||||||
| Chest pain | 1.2 | 3.4 | 2.0 | 1.8 | |||||
| Dizziness | 1.2 | 2.7 | 1.4 | 1.8 | |||||
| Fatigue | 1.9 | 1.9 | 1.4 | 2.8 | |||||
| Headache | 5.4 | 8.0 | 7.3 | 6.3 | |||||
Gastrointestinal system disorders Abdominal pain Diarrhea | 2.3 1.5 | 2.7 3.4 | 3.1 2.9 | 3.5 2.8 | |||||
| Infection and infestations | |||||||||
| Pharyngitis | 1.9 | 3.1 | 2.5 | 2.3 | |||||
| Sinusitis | 1.9 | 4.6 | 3.6 | 3.5 | |||||
| Upper respiratory tract infection | 10.8 | 13.0 | 13.6 | 11.8 | |||||
| Musculoskeletal system disorders | |||||||||
| Arthralgia | 2.3 | 3.8 | 4.3 | 3.4 | |||||
| Back pain | 3.5 | 3.4 | 3.7 | 4.3 | |||||
| Myalgia | 4.6 | 5.0 | 4.1 | 4.5 | |||||
* Includes four placebo-controlled combination studies in which ezetimibe was initiated concurrently with a statin. ** All statins = all doses of all statins. | |||||||||
In co-administration placebo-controlled clinical trials, 5.7% of patients treated with ezetimibe co-administered with a statin, 4.3% of patients treated with statin alone, 5.0% of patients treated with ezetimibe alone, and 6.2% of patients treated with placebo were withdrawn from therapy due to adverse events.
The following additional drug-related adverse experiences were reported in patients taking ezetimibe co-administered with a statin (n = 11,308) and at a greater incidence than statin administered alone (n=9361).
Uncommon (incidence ≥0.1% and <1%)
Gastrointestinal Disorders: dry mouth; gastritis
General Disorders: asthenia; edema peripheral
Musculoskeletal and Connective Tissue Disorders: muscular weakness; pain in extremity
Nervous System Disorders: paresthesia
Skin and Subcutaneous Tissue Disorders: pruritus; rash; urticaria
Abnormal Hematologic and Clinical Chemistry Findings
In controlled clinical monotherapy trials, the incidence of clinically important consecutive elevations in serum transaminases (ALT and/or AST ≥ 3 X ULN) was similar between ezetimibe (0.5%) and placebo (0.3%). In co-administration trials, the incidence was 1.3% for patients treated with ezetimibe co-administered with a statin and 0.4% for patients treated with a statin alone. These elevations were generally asymptomatic, not associated with cholestasis, and returned to baseline levels after discontinuation of therapy or with continued treatment.
In clinical trials there was no excess of myopathy or rhabdomyolysis associated with ezetimibe compared with the relevant control arm (placebo or statin alone). However, myopathy and rhabdomyolysis are known adverse reactions to statins and other lipid-lowering drugs. In clinical trials, the incidence of CK >10 X ULN was 0.2% for ezetimibe vs 0.1% for placebo, and 0.1% for ezetimibe co-administered with a statin vs 0.4% for statin alone.
Post-Market Adverse Drug Reactions
The following adverse events have been reported rarely or very rarely, regardless of causality:
- increased CK (creatine phosphokinase)
- myalgia (see WARNINGS AND PRECAUTIONS)
- myopathy/rhabdomyolysis (see WARNINGS AND PRECAUTIONS)
- elevations of liver transaminases
- hepatitis (see WARNINGS AND PRECAUTIONS)
- hypersensitivity reactions, including anaphylaxis, angioedema, rash and urticaria
- erythema multiforme
- nausea
- pancreatitis (see WARNINGS AND PRECAUTIONS)
- thrombocytopenia
- arthralgia
- dizziness
- cholelithiasis
- cholecystitis
- depression
- paresthesia
- constipation
- asthenia
DRUG INTERACTIONS
Serious Drug Interactions
|
Drug-drug interactions are known or suspected with cholestyramine, cyclosporine.
Drug-Drug Interactions
Cytochrome P450 System: No clinically significant pharmacokinetic interactions have been observed between ezetimibe and drugs known to be metabolized via CYP 1A2, 2D6, 2C8, 2C9, and 3A4 isoenzymes, or N-acetyltransferase such as caffeine, dextromethorphan, tolbutamide, and IV midazolam. It has been shown that ezetimibe neither induces, nor inhibits, these cytochrome P450 isoenzymes.
Anticoagulants: Concomitant administration of ezetimibe (10 mg once daily) had no significant effect on bioavailability of warfarin and prothrombin time in a study of twelve healthy adult males. As with the initiation of any medication in patients treated with warfarin or another coumarin anticoagulant, additional International Normalised Ratio (INR) measurements are recommended for patients administered warfarin or another coumarin anticoagulant concomitantly with ezetimibe.
Digoxin: Concomitant administration of ezetimibe (10 mg once daily) had no significant effect on the bioavailability of digoxin and the ECG parameters (HR, PR, QT, and QTc intervals) in a study of twelve healthy adult males.
Oral Contraceptives: Co-administration of ezetimibe (10 mg once daily) with oral contraceptives had no significant effect on the bioavailability of ethinyl estradiol or levonorgestrel in a study of eighteen healthy adult females.
Cimetidine: Multiple doses of cimetidine (400 mg twice daily) had no significant effect on the oral bioavailability of ezetimibe and total ezetimibe in a study of twelve healthy adults.
Antacids: Concomitant antacid (aluminum and magnesium hydroxide) administration decreased the rate of absorption of ezetimibe but had no effect on the bioavailability of ezetimibe. This decreased rate of absorption is not considered clinically significant.
Glipizide: In a study of twelve healthy adult males, steady-state levels of ezetimibe (10 mg once daily) had no significant effect on the pharmacokinetics and pharmacodynamics of glipizide. A single dose of glipizide (10 mg) had no significant effect on the exposure to total ezetimibe or ezetimibe.
Cholestyramine: Concomitant cholestyramine administration decreased the mean AUC of total ezetimibe (ezetimibe + ezetimibe-glucuronide) approximately 55%. The incremental LDL-C reduction due to adding ezetimibe to cholestyramine may be lessened by this interaction.
Statins: No clinically significant pharmacokinetic interactions were seen when ezetimibe was co-administered with atorvastatin, simvastatin, pravastatin, lovastatin, fluvastatin or rosuvastatin. Co-administration of ezetimibe with all fibrates has not been studied. Fibrates may increase cholesterol excretion into the bile, leading to cholelithiasis. In a preclinical study in dogs, ezetimibe increased cholesterol in the gallbladder bile. Although the relevance of this preclinical finding to humans is unknown, co-administration of ezetimibe with fibrates is not recommended until use in patients is studied.
Cyclosporine: Caution should be exercised when initiating ezetimibe in the setting of cyclosporine. Cyclosporine concentrations should be monitored in patients receiving ezetimibe and cyclosporine.
In a study of eight post-renal transplant patients with creatinine clearance of >50 mL/min on a stable dose of cyclosporine, a single 10 mg dose of ezetimibe resulted in a 3.4-fold (range 2.3- to 7.9-fold) increase in the mean AUC for total ezetimibe compared to a healthy control population from another study (n=17). In a different study, a renal transplant patient with severe renal insufficiency (creatinine clearance of 13.2 mL/min/1.73 m2) who was receiving multiple medications, including cyclosporine, demonstrated a 12-fold greater exposure to total ezetimibe compared to concurrent controls.
In contrast, in a two-period crossover study in twelve healthy subjects, daily administration of 20 mg ezetimibe for 8 days with a single 100-mg dose of cyclosporine on Day 7 resulted in a mean 15% increase in cyclosporine AUC (range 10% decrease to 51% increase) compared to a single 100-mg dose of cyclosporine alone.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Patients should be placed on a standard cholesterol-lowering diet at least equivalent to the NCEP Adult Treatment Panel III (ATP III) TLC diet before receiving ACT EZETIMIBE, and should continue on this diet during treatment with ACT EZETIMIBE. If appropriate, a program of weight control and physical exercise should be implemented.
- Prior to initiating therapy with ACT EZETIMIBE, secondary causes for elevations in plasma lipid levels should be excluded. A lipid profile should also be performed.
Recommended Dose and Dosage Adjustment
The recommended dose of ACT EZETIMIBE is 10 mg once daily orally, alone, or with a statin. ACT EZETIMIBE can be taken with or without food at any time of the day but preferably at the same time each day.
Use in the Elderly: No dosage adjustment is required for elderly patients (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
Use in Pediatric Patients: Children and adolescents ≥ 10 years: No dosage adjustment is required (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
Use in Patients with Hepatic Impairment: No dosage adjustment is required in patients with mild hepatic insufficiency (Child-Pugh score 5 to 6). Treatment with ACT EZETIMIBE is not recommended in patients with moderate (Child-Pugh score 7 to 9) or severe (Child-Pugh score >9) liver dysfunction (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Patients with Liver Impairment).
Use in Patients with Renal Impairment: No dosage adjustment is required for patients with renal impairment (see WARNINGS AND PRECAUTIONS, Renal, Renal Insufficiency).
Co-administration with Bile Acid Sequestrants: ACT EZETIMIBE should be administered either 2 hours or longer before or 4 hours or longer after administration of a bile acid sequestrant (see DRUG INTERACTIONS, Drug-Drug Interactions, Cholestyramine).
Missed Dose
The recommended dosing regimen is one tablet, once daily. If a dose is missed, the patient should be counselled to resume the usual schedule of one tablet daily.
OVERDOSAGE
In clinical studies, administration of ezetimibe, 50 mg/day to 15 healthy subjects for up to 14 days, or 40 mg/day to 18 patients with primary hypercholesterolemia for up to 56 days, was generally well tolerated.
A few cases of overdosage with ezetimibe have been reported; most have not been associated with adverse experiences. Reported adverse experiences have not been serious. In the event of an overdose, symptomatic and supportive measures should be employed.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ezetimibe is in a new class of lipid-lowering compounds that selectively inhibit the intestinal absorption of cholesterol and related plant sterols. Ezetimibe is orally active, with a unique mechanism of action that differs from other classes of cholesterol-reducing compounds e.g., HMG-CoA reductase inhibitors (statins), bile acid sequestrants (resins), fibric acid derivatives, plant stanols. The molecular target of ezetimibe is the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is responsible for the intestinal uptake of cholesterol and phytosterols.
Although ezetimibe is rapidly absorbed and is extensively metabolized to an active phenolic glucuronide which reaches the systemic circulation after oral administration (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Absorption), its action is localized at the brush border of the small intestine where it inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver. This results in a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood. Ezetimibe does not increase bile acid excretion in contrast to bile acid sequestrants and does not inhibit cholesterol synthesis in the liver as do statins. Ezetimibe and statins have distinct mechanisms of action that provide complementary cholesterol reduction.
Clinical studies have demonstrated that elevated levels of total-C, low density lipoprotein cholesterol (LDL-C) and apolipoprotein B (Apo B; the major protein constituent of LDL), promote atherosclerosis in humans. In addition, decreased levels of high density lipoprotein cholesterol (HDL-C) are associated with the development of atherosclerosis. Epidemiologic studies have established that cardiovascular morbidity and mortality vary directly with the level of total-C and LDL-C and inversely with the level of HDL-C. Like LDL, cholesterol-enriched triglyceride-rich lipoproteins, including very low density lipoproteins (VLDL), intermediate density lipoproteins (IDL), and remnants, can also promote atherosclerosis. The effects of ezetimibe given either alone or in addition to a statin on cardiovascular morbidity and mortality have not been established.
Pharmacodynamics
Preclinical studies in animals were performed to determine the selectivity of ezetimibe for inhibiting cholesterol absorption. Ezetimibe inhibited the absorption of [14C]-cholesterol with no effect on the absorption of triglycerides, fatty acids, bile acids, progesterone, ethinyl estradiol, or the fat soluble vitamins A and D.
In a study of hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E, and did not impair adrenocortical steroid hormone production.
Pharmacokinetics
Absorption
After oral administration, ezetimibe is rapidly absorbed and extensively conjugated to a phenolic glucuronide (ezetimibe-glucuronide) form which is at least as pharmacologically active as the parent drug. Mean ezetimibe peak plasma concentrations (Cmax) of 3.4 to 5.5 ng/mL were attained within 4 to 12 hours (Tmax). Ezetimibe-glucuronide mean Cmax values of 45 to 71 ng/mL were achieved between 1 and 2 hours (Tmax). The extent of absorption and absolute bioavailability of ezetimibe cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection.
Concomitant food administration (high fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as ezetimibe 10 mg tablets. Cmax of ezetimibe was increased by 38% when taken with high fat meals.
Distribution
Ezetimibe and ezetimibe-glucuronide are bound 99.7% and 88 to 92% to human plasma proteins, respectively.
Metabolism
Ezetimibe is metabolized primarily in the small intestine and liver via glucuronide conjugation (a phase II reaction) with subsequent biliary and renal excretion. Minimal oxidative metabolism (a phase I reaction) has been observed in all species evaluated. Ezetimibe and ezetimibeglucuronide are the major compounds detected in plasma. The conjugated ezetimibeglucuronide constitutes 80-90% of plasma drug levels with ezetimibe the remaining 10-20%. Both ezetimibe and ezetimibe-glucuronide are slowly eliminated from plasma with evidence of significant enterohepatic recycling. The half-life for ezetimibe and ezetimibe-glucuronide is approximately 22 hours.
Excretion
Following oral administration of 14C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma. Approximately 78% and 11% of the administered radioactivity were recovered in the faeces and urine, respectively, over a 10-day collection period. After 48 hours, there were no detectable levels of radioactivity in the plasma. Ezetimibe was the major component in faeces (69% of the administered dose) while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose.
STORAGE AND STABILITY
Store between 15°C and 30°C. Protect from moisture.
DOSAGE FORMS, COMPOSITION AND PACKAGING
ACT EZETIMIBE is available as a 10 mg tablet for oral administration.
ACT EZETIMIBE is formulated as white to off-white, capsule-shaped tablets debossed with “713" on one side and plain on the other side. Each tablet contains 10 mg of active ingredient, ezetimibe.
Non-medicinal ingredients: Lactose monohydrate, croscarmellose sodium, hypromellose, sodium lauryl sulfate, crospovidone, microcrystalline cellulose and magnesium stearate.
ACT EZETIMIBE tablets are available in a carton of 30s (3 x 10 UD blisters).
ACT EZETIMIBE tablets are also available in HDPE bottles of 100 (bottle includes a desiccant).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
| Solvent | Solubility (mg/mL) Ambient temperature (about 23°C) | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| Ezetimibe anhydrous | Ezetimibe hydrate | ||||||||
| Water | 0.012 | 0.008 | |||||||
| 0.1 N HCl | 0.011 | 0.024 | |||||||
| n-hexane | <0.001 | <0.001 | |||||||
| Acetonitrile | 68.6 | 77.8 | |||||||
| Methanol | >200 | not determined | |||||||
| Acetone | >200 | not determined | |||||||
| DMSO | >200 | not determined | |||||||
| Ethanol (USP) | 168 | 169 | |||||||
| Ethanol: 0.1N HCl (1:1) | 1.7 | 1.8 | |||||||
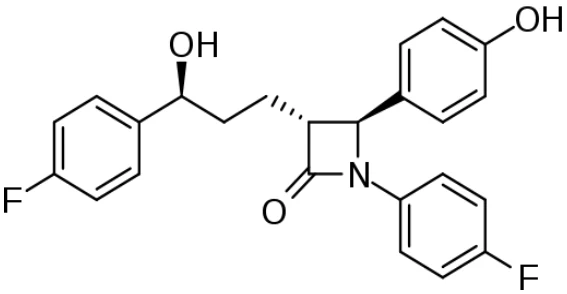
| Drug Substance | ||
| Common name: | Ezetimibe | |
| Chemical name: | (3R,4S)-1-(4-fluorophenyl)-3-[(3S)-3-(4-fluorophenyl) -3-hydroxypropyl]-4-(4-hydroxyphenyl)-2-azetidinone | |
| Molecular formula: | C24H21F2NO3 | |
| Molecular mass: | 409.42 g/mol | |
| Structural formula: | ||
| Physicochemical properties: | ||
| Physical form: | White to off-white crystalline powder. | |
| Solubility: | Ezetimibe is freely soluble in methanol and acetone, soluble in ethanol, practically insoluble in water. | |
| Solvent | Solubility (mg/mL) Ambient temperature (about 23°C) |
|---|
| Ezetimibe anhydrous | Ezetimibe hydrate | |
|---|---|---|
| pH 4.5 phosphate buffer (0.05M) with 1% sodium lauryl sulfate | 0.16 | 0.16 |
| pH 4.5 acetate buffer (0.05M) with 0.45% sodium lauryl sulfate | 0.054 | not determined |
| pKa: | 9.75 (potentiometric titration) 9.66 (theoretical) | |
| pH | 6.0 (1.0% w/v aqueous suspension at 25°C) | |
Partition Coefficient: n-octanol/0.1N HCl n-octanol/pH 7 buffer | Log Ko/w=4.52 Log Ko/w=4.51 | |
| (Ko/w = Korganic phase/water phase) | ||
| Melting point: | 164.16°C (by DSC) | |
CLINICAL TRIALS
Comparative Bioavailability Studies
A randomized, blinded, two treatment, two period, two sequence, single dose crossover bioequivalence study of ACT EZETIMIBE Tablets, 10 mg (Actavis Pharma Company, Canada) and PrEzetrol® (Ezetimibe tablets) 10 mg manufactured by Merck Frosst- Schering Pharma (G.P./S.E.N.C), Canada was conducted in healthy adult male subjects under fasting conditions. A summary of the bioavailability data from 36 subjects is presented in the table below.
| SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA | ||||
|---|---|---|---|---|
Ezetimibe (Unconjugated) (1 x 10 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 80.0 86.3 (37.8) | 86.3 96.3 (45.2) | 92.7 | 84.5 - 101.7 |
AUCI ** (ng.h/mL) | 89.6 97.2 (45.1) | 97.8 104.9 (41.4) | 91.6 | 84.2 - 99.7 |
Cmax (ng/mL) | 5.4 6.1 (54.5) | 5.9 6.8 (62.9) | 90.1 | 80.1- 101.4 |
Tmax € (h) | 6.6 (57.0) | 5.8 (48. 5) | ||
T½€ ** (h) | 15.6 (50.9) | 14.3 (37.9) | ||
* ACT EZETIMIBE Tablets, 10 mg (Actavis Pharma Company, Canada)
† Pr EZETROL® (Ezetimibe Tablets), 10 mg manufactured by Merck Frosst- Schering Pharma (G.P./S.E.N.C)was purchased in Canada
** Arithmetic means: n=34 subjects for Test; n=31 subjects for Reference
AUC I geometric mean ratio and confidence interval for n=29 subjects
€ Expressed as the arithmetic mean (CV%) only.
Safety and Efficacy Trials
Primary Hypercholesterolemia
Ezetimibe Tablets (ezetimibe) has been shown to be effective in reducing total-C, LDL-C, Apo B, and TG and increasing HDL-C in patients with primary hypercholesterolemia. Maximal to near maximal response is generally achieved within 2 weeks and maintained during chronic therapy.
Ezetimibe is effective in a variety of patient populations with hypercholesterolemia, in men and women, and in the elderly, administered alone or with a statin.
Monotherapy
In two double-blind, placebo-controlled studies of 12 weeks duration in patients with primary hypercholesterolemia, ezetimibe significantly lowered total-C, LDL-C, Apo B, and TG and increased HDL-C compared with placebo. The studies enrolled 1719 patients (ezetimibe=1288, placebo=431) with an LDL-C ≥ 130 mg/dL (3.37 mmol/L) and ≤ 250 mg/dL (6.48 mmol/L), and with a TG ≤ 350 mg/dL (3.96 mmol/L). In general, the groups were balanced with regard to body weight, sex, age, race and baseline lipid levels; at entry into the study the mean LDL-C was 165 mg/dL (4.27 mmol/L) while the mean age was 58 years and 48% were male.
Reductions in LDL-C were consistent across age, sex, race, and baseline LDL-C (see Table 3). In addition, ezetimibe had no effect on the plasma concentrations of the fat-soluble vitamins A, D, and E, or on prothrombin time, and did not impair adrenocortical steroid hormone production.
| Table 3 - Mean Response to Ezetimibe in Patients with Primary Hypercholesterolemia (Mean % Change from Baseline) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Treatment Group | N | Total-C | LDL-C | Apo B | TGa | HDL-C | |||||||
| Study 1 | Placebo | 205 | +1 | +1 | -1 | -1 | -1 | ||||||
| Ezetimibe | 622 | -12 | -18 | -15 | -7 | +1 | |||||||
| Study 2 | Placebo | 226 | +1 | +1 | -1 | +2 | -2 | ||||||
| Ezetimibe | 666 | -12 | -18 | -16 | -9 | +1 | |||||||
| a Median % change from baseline | |||||||||||||
In two, 12 week ezetimibe monotherapy studies which included 1288 patients treated with ezetimibe and 431 treated with placebo, the safety profile of ezetimibe was similar to that of placebo. There was no difference in the incidence of clinically important liver function or muscle adverse experiences between the groups.
Co-Administration with a Statin
Ezetimibe Initiated Concurrently with a Statin
In four double-blind, placebo-controlled studies in patients with primary hypercholesterolemia, ezetimibe co-administered with a statin significantly lowered total-C, LDL-C, Apo B and TG and increased HDL-C compared with a statin alone. The studies enrolled 2382 patients (ezetimibe alone=262, placebo=259, ezetimibe co-administered with a statin=925, statin alone=936) with an LDL-C ≥ 145 mg/dL (3.76 mmol/L) and ≤ 250 mg/dL (6.48 mmol/L) and with TG ≤ 350 mg/dL (3.96 mmol/L). In general, the groups were balanced with regard to body weight, sex, age, race and baseline lipids; at entry into the study the mean LDL-C was 179 mg/dL (4.64 mmol/L) while the mean age was 57 years and 43% were male.
In general, the incremental effect on LDL-C reduction was independent of the dose or specific statin used. In addition, LDL-C reduction for ezetimibe co-administered with the lowest tested dose (10 mg) of any of the statins was similar to or greater than the LDL-C reduction of the highest tested dose of the corresponding statin administered alone (Table 4).
| Table 4 - Mean % Change from Baseline in Plasma Concentration of Calculated LDL-C for Ezetimibe Administered with Statins | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Atorvastatin Study | Simvastatin Study | Pravastatin Study | Lovastatin Study | ||||||
| Placebo | +4 | -1 | -1 | 0 | |||||
| Ezetimibe | -20 | -19 | -20 | -19 | |||||
| Table 4 - Mean % Change from Baseline in Plasma Concentration of Calculated LDL-C for Ezetimibe Administered with Statins |
|---|
| Atorvastatin Study | Simvastatin Study | Pravastatin Study | Lovastatin Study | |
|---|---|---|---|---|
| 10 mg statin | -37 | -27 | -21 | -20 |
| Ezetimibe + 10 mg statin | -53 | -46 | -34 | -34 |
| 20 mg statin | -42 | -36 | -23 | -26 |
| Ezetimibe + 20 mg statin | -54 | -46 | -40 | -41 |
| 40 mg statin | -45 | -38 | -31 | -30 |
| Ezetimibe + 40 mg statin | -56 | -56 | -42 | -46 |
| 80 mg statin | -54 | -45 | - | - |
| Ezetimibe + 80 mg statin | -61 | -58 | - | - |
In addition, ezetimibe had a beneficial effect on total-C, Apo B, TG, and HDL-C.
In the 4 ezetimibe and statin factorial studies performed with lovastatin, pravastatin, simvastatin and atorvastatin, 925 patients received ezetimibe co-administered with statins and 936 received statin alone. Overall, the co-administration of ezetimibe and statin was well tolerated. There was no difference in the incidence of clinically important muscle adverse experiences. There was small excess of liver function elevations in the co-administration group compared to statins alone: 1.3% vs 0.4% respectively.
Ezetimibe Added to On-going Statin Therapy
In a single double-blind, placebo-controlled study of 8 weeks duration in patients with primary hypercholesterolemia, with known coronary artery disease or multiple cardiovascular risk factors not controlled by existing statin therapy (i.e., LDL-C exceeded NCEP ATP II defined targets), the addition of ezetimibe to a statin further reduced LDL-C by 25% (vs 4% for statin alone) and brought significantly more patients to their LDL-C goal than the statin alone (72% vs 19%). The study enrolled 769 patients (ezetimibe co-administered with a statin=379, statin alone=390). In general, the groups were balanced with regard to body weight, sex, age, race and baseline lipids; at entry into the study the mean LDL-C was 139 mg/dL (3.60 mmol/L) while the mean age was 60 years and 58% were male.
Homozygous Familial Hypercholesterolemia (HoFH)
A study was conducted to assess the efficacy of ezetimibe in the treatment of HoFH. This double-blind, randomized, 12-week study enrolled 50 patients with a clinical and/or genotypic diagnosis of HoFH, with or without concomitant LDL apheresis. Patients were already receiving atorvastatin or simvastatin (40 mg) at entry, had LDL-C ≥ 100 mg/dL (2.59 mmol/L), and were randomized to one of three treatment groups: atorvastatin or simvastatin (80 mg; n=17), ezetimibe administered with atorvastatin or simvastatin (40 mg) or ezetimibe administered with atorvastatin or simvastatin (80 mg; n=33). In general, the groups were well balanced with regard to body weight, sex, age, race and baseline lipids; at entry into the study the mean LDL-C was 332 mg/dL (8.60 mmol/L), the mean age was 32 years and 42% were male.
Ezetimibe, administered with atorvastatin (40 mg or 80 mg) or simvastatin (40 mg or 80 mg), significantly reduced LDL-C compared with increasing the dose of simvastatin or atorvastatin monotherapy from 40 mg to 80 mg.
| Table 5 - Mean Response to Ezetimibe in Patients with HoFH (Mean % Change from Baseline) | |||
| Treatment (Daily Dose) | N | LDL-C | |
| Atorvastatin (80 mg) or simvastatin (80 mg) | 17 | -7 | |
| Ezetimibe + atorvastatin (40 mg or 80 mg) or simvastatin (40 mg or 80 mg) | 33 | -21 | |
Sub-group analysis: Ezetimibe + atorvastatin (80 mg) or simvastatin (80 mg) | 17 | -27 | |
Homozygous Sitosterolemia (Phytosterolemia)
A study was conducted to assess the efficacy of ezetimibe as adjunctive therapy in the treatment of homozygous sitosterolemia. This multicenter, double-blind, placebo-controlled, study of 8-weeks duration enrolled 37 patients (ezetimibe=30, placebo=7) ≥ 10 years of age with sitosterol >5 mg/dL (0.1 mmol/L). In general, the groups were well balanced with regard to body weight, sex, age, race and baseline lipids; at entry into the study the mean sitosterol was 20 mg/dL (0.5 mmol/L), the mean age was 37 years and 35% were male.
Ezetimibe significantly lowered the two major plant sterols, sitosterol and campesterol, by 21% and 24% from baseline, respectively. In contrast, patients who received placebo had increases in sitosterol and campesterol of 4% and 3% from baseline, respectively. For patients treated with ezetimibe, the reduction in plant sterols was progressive over the course of the study.
Reductions in sitosterol and campesterol were consistent between patients taking ezetimibe concomitantly with bile acid sequestrants (n=8) and patients not on concomitant bile acid sequestrant therapy (n=21).
TOXICOLOGY
Acute Toxicity
The acute toxicity of ezetimibe following single doses was evaluated in mice, rats, and dogs.
| Table 6 - Ezetimibe LD50 Values | |||||||
| Species | Sex | Route | Estimated LD50 Value (mg/kg) | ||||
| Mouse | Male/Female | PO | >5000 | ||||
| Mouse | Male/Female | IP | >1000 LD50 <2000 | ||||
| Rat | Male/Female | PO | >5000 | ||||
| Rat | Male/Female | IP | >2000 | ||||
| Dog | Male/Female | PO | >3000 | ||||
| PO=orally; IP=intraperitoneally |
In animals, no toxicity was observed after single oral doses of 5000 mg/kg of ezetimibe in rats and mice and 3000 mg/kg in dogs.
Ezetimibe (1000 mg/kg) was co-administered with either simvastatin (1000 mg/kg) or lovastatin (1000 mg/kg) by oral gavage to mice and rats. All animals survived. There were no clinical observations of toxicity and no effects on body weight parameters. The estimated oral LD50 for both species was >1000 mg/kg of each co-administered agent.
Chronic Toxicity (ezetimibe alone)
Ezetimibe was well tolerated by mice, rats and dogs. No target organs of toxicity were identified in chronic studies at daily doses up to 1500 and 500 mg/kg in male and female rats, respectively, up to 500 mg/kg in mice, or up to 300 mg/kg in dogs.
Subchronic Toxicity (Ezetimibe/Statin Co-administration)
The safety of concomitant administration of ezetimibe and statins was assessed in rats and dogs in multiple dose toxicity studies ranging from 2 weeks to 3 months in duration. Target organs identified in these studies are summarized in the following table.
| Table 7 - Target Organs Affected in Animal Co-administered Ezetimibe and Statinsa | |
|---|---|
| Rat | Dog |
| Liverb :increased weight, hepatocellular vacuolation, hepatocellular hypertrophy, foci of cellular alteration, bile duct hyperplasia, increased liver-related serum enzymes | Liverb : decreased weight, bile duct hyperplasia, increased liver-related serum enzymes |
| Skeletal Muscleb : myofiber degeneration/regeneration, mixed cellular infiltration | Testesb : spermatic aggregates, spermatogenic alteration, luminal cellular debris |
| Stomach (nonglandular)b : hyperkeratosis, acanthosis, mixed cellular infiltration | |
a Ezetimibe was co-administered with simvastatin, lovastatin, pravastatin or atorvastatin. b Known target organ of statins. | |
When ezetimibe was co-administered with statins (specifically atorvastatin, simvastatin, pravastatin or lovastatin) toxicologic findings were consistent with those seen with statins administered alone. Co-administration of ezetimibe and statins did not result in any new toxicities.
Myopathy in rats was attributed to a toxicokinetic interaction resulting in increased systemic exposure to the statin (1.5- to 15.1 -fold) and/or its pharmacologically active metabolite (2.4- to 11.2 -fold) compared to the statin control. Similar alterations in plasma drug levels are not seen at lower doses (~10-20 times human exposure to total ezetimibe), and no myopathy in rats is seen under these conditions. Thus, ezetimibe does not increase the sensitivity of rats to statin-induced myopathy in the absence of a toxicokinetic interaction.
Co-administration of ezetimibe and statins to dogs was associated with marked (100x) increases in serum ALT activity. However, there was no evidence of necrosis in liver or skeletal muscle. Upon cessation of dosing, ALT values approached or returned to baseline within one month. Increases in ALT were attenuated by mevalonate, the product of HMG-CoA reductase, demonstrating that these increases were related to inhibition of the reductase. While the source of the ALT has not been identified, these changes in dogs were not indicative of drug-induced organ toxicity, based on the lack of any functional or morphologic changes in the liver that would typically be associated with transaminase increases of this magnitude.
Findings potentially relevant to the safety of concomitant administration of ezetimibe and statin in humans (i.e., hepatotoxicity, myopathy, and testicular degeneration) are similar to those of HMG-CoA reductase inhibitors administered alone.
Carcinogenicity
In two-year studies conducted in mice and rats, ezetimibe was not carcinogenic. A 104-week oral carcinogenicity study with ezetimibe was conducted in mice at doses up to 500 mg/kg (>150 times the human exposure at 10 mg daily based on AUC0-24hr for total ezetimibe). A 104-week oral carcinogenicity study with ezetimibe was conducted in rats at doses up to 1500 mg/kg (males) and 500 mg/kg (females) (~14 and ~17 times the human exposure at 10 mg daily based on AUC0-24hr for total ezetimibe). There were no statistically significant increases in tumor incidences in drug-treated rats or mice.
Mutagenicity
No evidence of mutagenicity was observed in vitro in a microbial mutagenicity (Ames) test with salmonella typhimurium and escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with or without metabolic activation. In addition, there was no evidence of genotoxicity in the in vivo mouse micronucleus test.
Combinations of ezetimibe and statins were not mutagenic (with or without metabolic activation), did not induce chromosome aberration (with or without exogenous metabolic activation) and did not induce an increase in micronuclei in mouse bone marrow polychromatic erythrocytes.
Reproductive and Teratogenicity Studies
In oral (gavage) fertility studies of ezetimibe conducted in rats, there was no evidence of reproductive toxicity at doses up to 1000 mg/kg/day in male or female rats (~1181 [males] times the human dose at 10 mg daily based on surface area and ~7 [females] times the human exposure at 10 mg daily based on AUC0-24hr for total ezetimibe). Ezetimibe, at doses up to 1000 mg/kg (the highest feasible dose), was not maternotoxic in embryo-fetal development studies in rats and rabbits.
Ezetimibe was not teratogenic in rats or rabbits and had no effect on prenatal or postnatal development. When ezetimibe was given with lovastatin, simvastatin, pravastatin or atorvastatin, no teratogenic effects were observed in embryo-fetal development studies in pregnant rats. In pregnant rabbits, a low incidence of skeletal malformations (fused sternebrae, fused caudal vertebrae, reduced number of caudal vertebrae) was observed when ezetimibe (1000 mg/kg; ≥ 146 times the human exposure at 10 mg daily based on AUC0-24hr for total ezetimibe) was administered with lovastatin (2.5 and 25 mg/kg), simvastatin (5 and 10 mg/kg), pravastatin (25 and 50 mg/kg), or atorvastatin (5, 25, and 50 mg/kg). Exposure to the pharmacologically active form of the statin ranged from 1.4 (atorvastatin) to 547 (lovastatin) times the human exposure at 10 mg daily (simvastatin or atorvastatin) or 20 mg daily (lovastatin and pravastatin) based on AUC0-24hr.
BIBLIOGRAPHY
- 1. Ballantyne CM, Houri J, Notarbartolo A, Melani L, Lipka LJ, Suresh R, et al for the Ezetimibe Study Group. Effect of ezetimibe coadministered with atorvastatin in 628 patients with primary hypercholesterolemia: a prospective, randomized, double-blind trial. Circulation 2003; 107:2409-15.
- 2. Ballantyne C, Van Heek M, Davis H, and Stone N. Evolving concepts: the role of ezetimibe in the management of hypercholesterolaemia. Eur Heart J Supplements 2002;4(Suppl J):J1-J24.
- 3. Bays H. Ezetimibe. Expert Opin Investig Drugs 2002;11(11):1587-604.
- 4. Bays HE, Moore PB, Drehobl MA, Rosenblatt S, Toth PD, Dujovne CA, et al for the Ezetimibe Study Group. Effectiveness and tolerability of ezetimibe in patients with primary hypercholesterolemia: pooled analysis of two phase II studies [published erratum appears in Clin Ther 2001 Sep;23(9):1601]. Clin Ther 2001;23(8):1209-30.
- 5. Davidson MH, McGarry T, Bettis R, Melani L, Lipka LJ, LeBeaut AP, et al on behalf of the Ezetimibe Study Group. Ezetimibe coadministered with simvastatin in patients with primary hypercholesterolemia. JACC 2002;40(12):2125-34i.
- 6. Dujovne CA, Ettinger MP, McNeer JF, Lipka LJ, LeBeaut AP, Suresh R, et al for the Ezetimibe Study Group. Efficacy and safety of a potent new selective cholesterol absorption inhibitor, ezetimibe, in patients with primary hypercholesterolemia. Am J Cardiol 2002;90(10):1092-7.
- 7. Expert Panel On Detection; Evaluation; And Treatment Of High Blood Cholesterol In Adults. Executive summary of the third report of the national cholesterol education program (NCEP) expert panel on detection, evaluation, and treatment of high blood cholesterol in adults (Adult Treatment Panel III). JAMA 2001;285(19):2486-97.
- 8. Fodor JG, Frohlich JJ, Genest JJ Jr, McPherson PR. Recommendations for the management and treatment of dyslipidemia. Report of the Working Group on Hypercholesterolemia and Other Dyslipidemias. CMAJ 2000;162(10):1441-7.
- 9. Gagné C, Bays HE, Weiss SR, Mata P, Quinto K, Melino M, et al for the Ezetimibe Study Group. Efficacy and safety of ezetimibe added to ongoing statin therapy for treatment of patients with primary hypercholesterolemia. Am J Cardiol 2002;90(10):1084-91.
- 10. Gagné C, Gaudet D, Bruckert E for the Ezetimibe Study Group. Efficacy and safety of ezetimibe coadministered with atorvastatin or simvastatin in patients with homozygous familial hypercholesterolemia. Circulation 2002;105(21):2469-75.
- 11.
Garcia-Calvo M, Lisnock JM, Bull HG, Hawes BE, Burnett DA, Braun MP, et al. The target of ezetimibe is Niemann–Pick C1-Like 1 (NPC1L1). Proc. Natl. Acad. Sci. USA
2005;102(23):8132-8137.
- 12. Kastelein JJP & Van Dam MJ. A new role for combination therapy in lipid management. Br J Cardiol 2001;8(11):639-53 (passim).
- 13. Kerzner B, Corbelli J, Sharp S, Lipka LJ, Melani L, LeBeaut A, et al for the Ezetimibe Study Group. Efficacy and safety of ezetimibe coadministered with lovastatin in primary hypercholesterolemia. Am J Cardiol 2003;91(4):418-24.
- 14. Knopp RH, Gitter H, Truitt T, Bays H, Manion CV, Lipka LJ, et al for the Ezetimibe Study Group. Effects of ezetimibe, a new cholesterol absorption inhibitor, on plasma lipids in patients with primary hypercholesterolemia. Eur Heart J 2003; 24(8):729-41.
- 15. Kosoglou T, Meyer I, Veltri EP, Statkevich P, Yang B, Zhu Y, et al. Pharmacodynamic interaction between the new selective cholesterol absorption inhibitor ezetimibe and simvastatin. Br J Clin Pharmacol 2002;54(3):309-19.
- 16. Melani L, Mills R, Hassman D, Lipetz R, Lipka LJ, LeBeaut A, et al, for the Ezetimibe Study Group. Efficacy and safety of ezetimibe coadministered with pravastatin in patients with primary hypercholesterolemia: A prospective, randomized, double-blind trial. Eur Heart J 2003;24(8):717-28.
- 17. Pearson TA, Laurora I, Chu H, Kafonek S. The lipid treatment assessment project (L-TAP). A multicenter survey to evaluate the percentages of dyslipidemic patients receiving lipid-lowering therapy and achieving low-density lipoprotein cholesterol goals. Arch Intern Med 2000;160(4): 459-67.
- 18. Shepherd J. The role of the exogenous pathway in hypercholesterolaemia. Eur Heart J Supplements 2001;3(Suppl E):E2-E5.
- 19. Sudhop T, Lutjohann D, Kodal A, Igel M, Tribble DL, Shah S, et al. Inhibition of intestinal cholesterol absorption by ezetimibe in humans. Circulation 2002;106(15):1943-8.
- 20. Product Monograph for EZETROL® (Ezetimibe Tablets, 10 mg) Manufactured by: Merck Canada Inc., Control Number: 153192, Date of Preparation: March 06, 2012.