


Product Monograph - Juxtapid
RECENT MAJOR LABEL CHANGES
7 Warnings and Precautions, Reproductive Health: Female and Male Potential 03/2022
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................... 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 4
4.1 Dosing Considerations ............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 6
4.4 Administration .......................................................................................................... 8
4.5 Missed Dose ............................................................................................................ 8
5 OVERDOSAGE ................................................................................................................. 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .......................... 8
7 WARNINGS AND PRECAUTIONS ................................................................................... 9
7.1 Special Populations ............................................................................................... 11
7.1.1 Pregnant Women ............................................................................................ 11
7.1.2 Breast-feeding................................................................................................. 11
7.1.3 Pediatrics ........................................................................................................ 11
7.1.4 Geriatrics......................................................................................................... 12
8 ADVERSE REACTIONS ................................................................................................. 12
8.1 Adverse Reaction Overview .................................................................................. 12
8.2 Clinical Trial Adverse Reactions ............................................................................ 12
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 15
8.5 Post-Market Adverse Reactions ............................................................................ 17
9 DRUG INTERACTIONS .................................................................................................. 17
9.1 Serious Drug Interactions ...................................................................................... 17
9.2 Drug Interactions Overview ................................................................................... 17 9.3 Drug-Behavioural Interactions ............................................................................... 18
9.4 Drug-Drug Interactions .......................................................................................... 18
9.5 Drug-Food Interactions .......................................................................................... 20
9.6 Drug-Herb Interactions .......................................................................................... 21
9.7 Drug-Laboratory Test Interactions ......................................................................... 21
10 CLINICAL PHARMACOLOGY ....................................................................................... 21
10.1 Mechanism of Action ........................................................................................ 21
10.2 Pharmacodynamics ......................................................................................... 21
10.3 Pharmacokinetics............................................................................................. 21
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 22
12 SPECIAL HANDLING INSTRUCTIONS ......................................................................... 22
PART II: SCIENTIFIC INFORMATION ....................................................................................... 23
13 PHARMACEUTICAL INFORMATION ............................................................................ 23
14 CLINICAL TRIALS .......................................................................................................... 24
14.1 Clinical Trials by Indication .............................................................................. 24
15 MICROBIOLOGY ............................................................................................................ 28
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 28
PATIENT MEDICATION INFORMATION ................................................................................... 29
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JUXTAPID® (lomitapide capsules) is indicated as an adjunct to a low-fat diet and other lipid-lowering drugs, with or without LDL apheresis, to reduce low-density lipoprotein cholesterol (LDL-C) in adult patients with homozygous familial hypercholesterolemia (HoFH).
Due to its benefit-risk profile, the prescribing of JUXTAPID should be limited to physicians experienced in the diagnosis and treatment of familial hypercholesterolemia.
The effect of JUXTAPID on cardiovascular morbidity and mortality has not been determined.
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Clinical studies of JUXTAPID did not include sufficient numbers of patients with HoFH aged 65 years and over to determine whether they respond differently than younger patients. Other reported clinical experience has not identified differences in responses between elderly and younger patients.
2 CONTRAINDICATIONS
- Patients with moderate or severe hepatic impairment, including those with unexplained persistent abnormal liver function tests (see Hepatic Steatosis).
- Patients with a known significant, chronic bowel disease, such as inflammatory bowel disease or malabsorption (see 4 DOSAGE AND ADMINISTRATION).
- Concomitant administration of >20 mg daily simvastatin (40 mg daily is allowed for patients who have previously tolerated simvastatin 80 mg daily for at least one year without evidence of muscle toxicity) (see 9.4 Drug-Drug Interactions).
Concomitant use of JUXTAPID (lomitapide) with strong or moderate CYP 3A4 inhibitors (see
9.4 Drug-Drug Interactions).
- Pregnancy (see Pregnant Women).
- Patients with rare hereditary problems of galactose intolerance, the Lapp-lactase deficiency, or glucose-galactose malabsorption.
- Patients who are hypersensitive to JUXTAPID, or to any ingredient in the formulation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Treatment with JUXTAPID (lomitapide) should be initiated and monitored by a physician experienced in the treatment of familial hypercholesterolemia. JUXTAPID should be used as an adjunct to a low-fat diet and other lipid-lowering drugs, in the treatment of HoFH (see 1 INDICATIONS).
- Appropriate control of the fat content in the diet is essential to reduce the occurrence and severity of gastrointestinal side effects associated with the use of JUXTAPID. Patients should follow a diet supplying less than 20% of energy from fat prior to initiating JUXTAPID treatment, and should continue this diet during treatment. Dietary counseling should be provided.
- To reduce the risk of developing a fat-soluble nutrient deficiency due to JUXTAPID’s mechanism of action in the small intestine, patients treated with JUXTAPID should take daily dietary supplements that contain 400 international units vitamin E and at least 200 mg linoleic acid, 210 mg alpha linoleic acid (ALA), 110 mg eicosapentaenoic acid (EPA), and 80 mg docosahexaenoic acid (DHA). These dietary supplements should not be taken within a two hour window of JUXTAPID administration. For example, it may be convenient for dietary supplements to be taken in the morning.
- JUXTAPID should be taken without food (see 4.4 Administration). JUXTAPID administration with food increases systemic exposure to lomitapide (see 10.3 Pharmacokinetics). JUXTAPID administration with food may also increase the incidence of gastrointestinal adverse events, and so should be avoided.
- Concomitant Use with HMG-CoA Reductase Inhibitors: JUXTAPID increases plasma concentrations of statins. Dose reduction of statins may be required, especially with simvastatin, to mitigate risk of statin-induced myopathy, including rhabdomyolysis (see 2 CONTRAINDICATIONS, Concomitant Use with HMG-CoA Reductase Inhibitors, and 9 DRUG INTERACTIONS, Table 9).
- Cytochrome P450 3A4 Inhibitors: JUXTAPID is contraindicated with concomitant use of strong and moderate CYP 3A4 inhibitors (see 2 CONTRAINDICATIONS). When concomitantly used with atorvastatin, a weak CYP3A4 inhibitor, JUXTAPID should either be taken separately, i.e., 12 hours apart, or the dose of JUXTAPID should be reduced by 50%. When concomitantly used with any other weak CYP3A4 inhibitor, such as alprazolam, amiodarone, amlodipine, azithromycin, bicalutamide, cilostazol, cimetidine, cyclosporine, fluoxetine, fluvoxamine, ginkgo, goldenseal, isoniazid, lapatinib, nilotinib, oral contraceptives, pazopanib, peppermint oil, ranitidine, ranolazine, Seville oranges, ticagrelor, tolvaptan, and zileuton, separate the dose of the medications, i.e., JUXTAPID and the weak CYP 3A4 inhibitor, by 12 hours (see 9 DRUG INTERACTIONS). Consider limiting the maximum daily dose of JUXTAPID according to desired LDL-C response. Exercise additional caution if administering more than one (1) weak CYP3A4 inhibitor with JUXTAPID.
Grapefruit Juice: Patients taking JUXTAPID should avoid consumption of grapefruit juice
(see Concomitant Use of CYP 3A4 Inhibitors, and 9.5 Drug-Food Interactions).
P-glycoprotein (P-gp) Substrates: Lomitapide is an inhibitor of P-gp (see 9 DRUG
INTERACTIONS). Coadministration of lomitapide with P-gp substrates, such as, aliskiren, ambrisentan, colchicine, dabigatran etexilate, digoxin, everolimus, fexofenadine, imatinib, lapatinib, maraviroc, nilotonib, posaconazole, saxagliptin, sirolimus, sitagliptin, talinolol, tolvaptan, and topotecan, may increase absorption of P-gp substrates. Dose reduction of P-gp substrates should be considered when used concomitantly with lomitapide.
- Bile acid sequestrants: JUXTAPID has not been tested for interaction with bile acid sequestrants. Administration of JUXTAPID and bile acid sequestrants should be separated by at least 4 hours since bile acid sequestrants can interfere with the absorption of oral medications.
Warfarin: JUXTAPID increases the plasma concentrations of warfarin (see 9 DRUG
INTERACTIONS, Table 9). Increases in the dose of JUXTAPID may lead to supratherapeutic anticoagulation. Under circumstances when lomitapide dosage may be decreased, subtherapeutic anticoagulation may occur. Patients taking warfarin should undergo more frequent monitoring of the INR following initiation of lomitapide, or after dosage changes. It is suggested that INR be measured weekly, until a stable dose of JUXTAPID has been achieved for at least 2 weeks.
- Hepatic transaminases (ALT, AST), alkaline phosphatase, and total bilirubin should be measured before initiation of treatment with JUXTAPID (see Elevations in Hepatic Transaminases).
4.2 Recommended Dose and Dosage Adjustment
The dose of JUXTAPID should be escalated gradually to minimize the incidence and severity of gastrointestinal side effects. The recommended starting dose is 5 mg once daily. After 2 weeks, the dose may be increased, based on acceptable safety and tolerability, to 10 mg, and then, at a minimum of 4-week intervals, to 20 mg, 40 mg, and the maximum recommended dose of 60 mg as described in Table 1. Modify dosing for patients taking concomitant CYP 3A4 inhibitors, renal impairment, or baseline hepatic impairment.
Table 1: Recommended Regimen for Titrating Dosage
| DOSAGE | DURATION OF ADMINISTRATION BEFORE CONSIDERING INCREASE TO NEXT DOSAGE |
| 5 mg daily | At least 2 weeks |
| 10 mg daily | At least 4 weeks |
| 20 mg daily | At least 4 weeks |
| 40 mg daily | At least 4 weeks |
| 60 mg daily | Maximum recommended dosage |
During the first year, measure liver-related tests, especially ALT and/or AST, prior to each increase in dose or monthly, whichever occurs first. (see Elevations in Hepatic Transaminases).
Table 2 summarizes recommendations for dosage adjustment and monitoring for patients who develop elevated transaminases during therapy with JUXTAPID, see Table 2, below. Table 2: Dosage Adjustment and Monitoring in Patients with Elevated Transaminases
| ALT OR AST | TREATMENT AND MONITORING RECOMMENDATIONS* |
| ≥3x and <5x ULN |
|
| ≥5x ULN |
|
*Recommendations based on an ULN of approximately 30-40 international units/L.
If transaminase elevations are accompanied by clinical symptoms of liver injury (such as nausea, vomiting, abdominal pain, fever, jaundice, lethargy, flu-like symptoms), increases in bilirubin ≥2 x ULN, or active liver disease, discontinue treatment with JUXTAPID and investigate to identify the probable cause.
Consistent with its mechanism of action, increases in absolute hepatic fat content may be expected in patients treated with lomitapide (see Hepatic Steatosis, and 8 ADVERSE REACTIONS, Table 4). The long term consequences of hepatic steatosis associated with JUXTAPID treatment are unknown, including risk of progression to steatohepatitis, fibrosis and cirrhosis. Accordingly, baseline assessment of hepatic fibrosis should be carried out using appropriate imaging technology, and subsequently repeated on an intermittent basis. Baseline and subsequent intermittent assessment using laboratory markers of hepatic inflammation, as well as of fibrosis, should also be instituted to identify the potential development of steatohepatitis, fibrosis and cirrhosis.
Special Populations:
Pediatrics (< 18 years of age): The safety and effectiveness in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
Renal Impairment: Patients with end-stage renal disease receiving dialysis should not exceed 40 mg JUXTAPID daily. There are no data available to guide dosing in other patients with renal impairment.
Hepatic Impairment: Patients with mild hepatic impairment (Child-Pugh A) should not exceed 40 mg JUXTAPID daily (see 10 CLINICAL PHARMACOLOGY). JUXTAPID is contraindicated in patients with moderate to severe hepatic impairment (see 2 CONTRAINDICATIONS).
Women of Reproductive Potential: JUXTAPID is contraindicated during pregnancy (see 2 CONTRAINDICATIONS). Before initiating treatment in women of reproductive potential, the absence of pregnancy should be confirmed, appropriate advice on effective methods of contraception provided, and effective contraception initiated, as appropriate. Oral contraceptives are weak CYP3A4 inhibitors; dosing with lomitapide should be separated by 12 hours (see 9 DRUG INTERACTIONS). Patients taking estrogen-based oral contraceptives should be advised about possible loss of effectiveness due to diarrhea and/or vomiting. If the patient becomes pregnant while taking JUXTAPID, the patient should immediately stop taking JUXTAPID and contact their health professional.
4.4 Administration
JUXTAPID should be taken once a day with a glass of water, without food, at least 2 hours after the evening meal, because administration with food may adversely impact gastrointestinal tolerability of JUXTAPID.
Patients should swallow JUXTAPID capsules whole. Capsules should not be opened, crushed dissolved, or chewed.
4.5 Missed Dose
If a dose of JUXTAPID is missed, the normal dose should be taken at the usual time the next day. If dosing is interrupted for more than a week, the healthcare provider should be contacted before restarting treatment.
5 OVERDOSAGE
There is no specific treatment in the event of overdosage of JUXTAPID (lomitapide). In the event of overdose, the patient should be treated symptomatically and supportive measures instituted as required. Liver-related tests should be monitored. Hemodialysis is unlikely to be beneficial given that lomitapide is highly protein bound.
The maximum dose administered to human subjects in clinical studies was 200 mg lomitapide, as a single dose, without adverse consequences.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3: Dosage Forms, Strengths, Composition and Packaging
Dosage Forms:
JUXTAPID Capsules 5 mg:
Each capsule contains 6 mg lomitapide mesylate equivalent to 5 mg free base. Orange/orange hard gelatin capsule printed with black ink “A733” and “5 mg.”
| Route of | Dosage Form / | Non-medicinal Ingredients | ||||
| Administration | Strength/Composition | |||||
| oral | Capsule 5 mg, 10 mg, 20 mg | Gelatin, lactose white monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch, red iron oxide (5 mg and 10 mg only), silicon dioxide, sodium starch glycolate, titanium dioxide. | ||||
JUXTAPID Capsules 10 mg:
Each capsule contains 11 mg lomitapide mesylate equivalent to 10 mg free base. Orange/white hard gelatin capsule printed with black ink “A733” and “10 mg.”
JUXTAPID Capsules 20 mg:
Each capsule contains 23 mg lomitapide mesylate equivalent to 20 mg free base. White/white hard gelatin capsule printed with black ink “A733” and “20 mg.”
Packaging:
All strengths (5 mg, 10 mg and 20 mg) are available in bottles of 28 capsules.
7 WARNINGS AND PRECAUTIONS
General
Concomitant Use of CYP 3A4 Inhibitors
CYP 3A4 inhibitors increase the exposure of lomitapide, with strong inhibitors increasing exposure approximately 27-fold. Concomitant use of strong or moderate CYP 3A4 inhibitors with JUXTAPID (lomitapide) is contraindicated (see 2
CONTRAINDICATIONS). If treatment with strong or moderate CYP 3A4 inhibitors is unavoidable, JUXTAPID should be stopped during the course of treatment.
Grapefruit juice must be omitted from the diet during treatment with JUXTAPID.
Weak CYP3A4 inhibitors are expected to increase the exposure of lomitapide when taken simultaneously. When administered with atorvastatin, the dose of JUXTAPID should either be taken 12 hours apart or be decreased by half. The dose of JUXTAPID should be administered 12 hours apart from any other weak CYP3A4 inhibitor (see 9.4 Drug-Drug Interactions and 4 DOSAGE AND ADMINISTRATION).
Concomitant Use with HMG-CoA Reductase Inhibitors
JUXTAPID increases plasma concentrations of statins. The risk of myopathy, including rhabdomyolysis, is dose related with use of statins. Lomitapide approximately doubles the exposure to simvastatin (see 9.4 Drug-Drug Interactions, Table 9). Accordingly, it is recommended to reduce the dose of simvastatin by 50% when initiating JUXTAPID. While taking JUXTAPID, limit simvastatin dosage to 20 mg daily (or 40 mg daily for patients who have previously tolerated simvastatin 80 mg daily for at least one year without evidence of muscle toxicity) (see 2 CONTRAINDICATIONS).
The effect of lomitapide on the systemic exposure of other statins is less than that seen with simvastatin (see 9 DRUG INTERACTIONS, Table 9), and is dependent both on the dose of statin and that of lomitapide administered. Dose adjustment of statin may be required (see 4 DOSAGE AND ADMINISTRATION).
Use with Warfarin
Lomitapide increases the plasma concentrations of warfarin (see 9 DRUG INTERACTIONS, Table 9). Patients taking warfarin should undergo more frequent monitoring of the INR, especially after any changes in JUXTAPID dosage (see 4 DOSAGE AND ADMINISTRATION). As usual, the dose of warfarin should be adjusted as clinically indicated.
Gastrointestinal
Risk of Severe Diarrhea and Dehydration
Use of lomitapide has been associated with severe diarrhea and dehydration. Caution should be exercised in vulnerable patients (e.g., geriatric patients, or patients taking diuretics) due to the subsequent risk of hypovolemia and hypotension.
Hepatic/Biliary/Pancreatic
Hepatic Steatosis
Consistent with the mechanism of action of JUXTAPID, most treated patients exhibited increases in hepatic triglyceride content, with or without concomitant increases in hepatic transaminases. In an open-label Phase 3 study, 18 of 23 patients with HoFH developed hepatic steatosis, i.e., hepatic fat > 5.6%, as measured by nuclear magnetic resonance spectroscopy (NMRS). There was a mean increase in absolute hepatic fat content of 6% after both 26 weeks and 78 weeks of treatment, from a mean of 1% at baseline (see 8 ADVERSE REACTIONS). Clinical data suggest that hepatic fat accumulation is reversible after stopping treatment with JUXTAPID, generally over 4 to 6 weeks, but whether histological sequelae remain is unknown, especially after long-term use. The long term consequences of hepatic steatosis associated with JUXTAPID treatment are unknown, including risk of progression to steatohepatitis and cirrhosis.
Use with Hepatotoxic Agents
Caution should be exercised when JUXTAPID is co-administered with agents known to have a potential for hepatotoxicity, such as isotretinoin, amiodarone, acetaminophen in high doses, methotrexate, tetracyclines, and tamoxifen. The effect of concomitant administration of JUXTAPID with other hepatotoxic medications is unknown. More frequent monitoring of liver function tests may be warranted.
Alcohol Consumption
JUXTAPID should be used with caution in patients who consume alcohol because of its potential to induce or exacerbate hepatic injury, including steatosis. Limitation of alcohol use is warranted with JUXTAPID treatment, e.g., a limit of no more than one drink daily.
Monitoring and Laboratory Tests
Elevations in Hepatic Transaminases
Elevations in alanine and/or aspartate transaminases (ALT and/or AST) associated with JUXTAPID treatment are generally dose-dependent, asymptomatic, and reversible (see 8 ADVERSE REACTIONS). Liver enzyme changes occur most often during dose escalation, but may occur at any time during therapy. In clinical studies, there were no concomitant increases in serum bilirubin or alkaline phosphatase.
Hepatic transaminases, i.e., serum ALT, AST, should be measured before initiation of treatment with JUXTAPID, and prior to each dose escalation (see 4 DOSAGE AND ADMINISTRATION). After the patient has been stabilized on an individualized dose, transaminases should be measured periodically, i.e., monthly during the first year of treatment and every three months after the first year.
Reproductive Health: Female and Male Potential
Fertility
Lomitapide had no effect on fertility in rats at doses up to 5 mg/kg/day at systemic exposures estimated to be 4-times (females) and 5-times (males) higher than in humans at 60 mg based on AUC.
Teratogenic Risk
Patients should be advised that JUXTAPID may cause birth defects based on animal studies. Before initiating treatment in women of child-bearing potential, the absence of pregnancy should be confirmed, appropriate advice on effective methods of contraception provided, and effective contraception initiated (see 4 DOSAGE AND ADMINISTRATION). Oral contraceptives are weak CYP3A4 inhibitors; dosing with lomitapide should be separated by 12 hours (see 9 DRUG INTERACTIONS). Patients taking estrogen-based oral contraceptives should be advised about possible loss of effectiveness due to diarrhea and/or vomiting. Additional contraceptive measures should be used until resolution of symptoms. Patients should be advised to immediately contact their health professional and stop taking JUXTAPID if they become pregnant while taking JUXTAPID.
7.1 Special Populations
7.1.1 Pregnant Women
JUXTAPID is contraindicated during pregnancy because it may cause fetal harm when administered to a pregnant woman. There was no experience of pregnancy during clinical trials. Lomitapide was teratogenic in rats and ferrets at exposures estimated to be less than human therapeutic exposure at 60 mg (AUC = 67ng*h/mL) when administered during organogenesis. There was no evidence of teratogenicity in rabbits at 3 times the maximum recommended human dose (MRHD) of 60 mg based on body surface area. Embryo-fetal lethality was observed in rabbits at ≥ 6-times the MRHD. If JUXTAPID is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to a fetus.
7.1.2 Breast-feeding
It is not known whether lomitapide is excreted in human milk. Because many drugs are excreted in human milk and because of the potential for tumorigenicity shown for lomitapide in a 2-year mouse study, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness in pediatric patients have not been established.
7.1.4 Geriatrics
Clinical studies of JUXTAPID did not include sufficient numbers of patients with HoFH aged 65 years and over to determine whether they respond differently than younger patients. In general, dosing for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and concomitant drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Consistent with the mechanism of action of JUXTAPID (lomitapide), most treated patients exhibited gastrointestinal (GI) discomfort or other related GI adverse events (see 4 DOSAGE AND ADMINISTRATION and Gastrointestinal).
The most common adverse reactions were gastrointestinal, reported by 27 of 29 (93%) homozygous familial hypercholesterolemia (HoFH) patients. Adverse reactions reported by ≥8 (28%) patients in the HoFH clinical trial included diarrhea, nausea, vomiting, dyspepsia, and abdominal pain. Other common adverse reactions, reported by 5 to 7 (17-24%) patients, included weight loss, abdominal discomfort, abdominal distension, constipation, flatulence, increased ALT, chest pain, influenza, nasopharyngitis, and fatigue.
Five of the 29 (17%) HoFH patients who participated in the JUXTAPID pivotal registration trial discontinued treatment due to an adverse reaction. The adverse reactions that contributed to treatment discontinuations were: diarrhea (2 patients); abdominal pain, nausea, gastroenteritis, weight loss, headache, and difficulty controlling INR on warfarin (1 patient each).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
A total of 999 patients have been treated with JUXTAPID in 25 clinical studies, including 22 exposed for 1 year. Due to the rarity of the disease, a single pivotal registration trial was conducted in patients with HoFH. It was a single-arm, open-label study in 29 patients. Patients treated with JUXTAPID in this study included 16 males (55%) and 13 females (45%); mean age of the population was 30.7 years, and ranged from 18 to 55 years.
The common (≥10%) adverse events reported in patients with HoFH in the pivotal registration trial are presented in Table 4.
Table 4: Adverse Events Reported in ≥10% (≥3 subjects) of HoFH Patients (N=29)
| ADVERSE REACTION | N (%) |
| Gastrointestinal Disorders | |
| Diarrhea | 23 (79) |
| Nausea | 19 (65) |
| Dyspepsia | 11 (38) |
| Vomiting | 10 (34) |
| Abdominal pain | 10 (34) |
| Abdominal discomfort | 6 (21) |
| Abdominal distension | 6 (21) |
| Constipation | 6 (21) |
| Flatulence | 6 (21) |
| Gastroesophageal reflux disease | 3 (10) |
| Defecation urgency | 3 (10) |
| Rectal tenesmus | 3 (10) |
| Infections | |
| Influenza | 6 (21) |
| Nasopharyngitis | 5 (17) |
| Gastroenteritis | 4 (14) |
| Investigations | |
| Decreased weight | 7 (24) |
| Increased ALT | 5 (17) |
| General Disorders | |
| Chest pain | 7 (24) |
| Fatigue | 5 (17) |
| Fever | 3 (10) |
| Musculoskeletal Disorders | |
| Back pain | 4 (14) |
| Nervous System Disorders | |
| Headache | 3 (10) |
| Dizziness | 3 (10) |
| Respiratory Disorders | |
| Pharyngolaryngeal pain | 4 (14) |
| Nasal congestion | 3 (10) |
| Cardiac Disorders | |
| Angina pectoris | 3 (10) |
| Palpitations | 3 (10) |
Adverse reactions of severe intensity were reported by 8 (28%) of 29 patients, with the most common being diarrhea (4 patients, 14%), vomiting (3 patients, 10%), increased ALT or hepatotoxicity (3 patients, 10%), and abdominal pain, distension, and/or discomfort (2 patients, 7%).
Non-HoFH Patient Population
Results from a pooled safety analysis of patients without HoFH but with elevated LDL-C and other cardiovascular risk factors demonstrated a similar pattern of adverse events (see Table 5) to that observed in HoFH patients (see Table 4). This pool comprises patients that were treated for multiple durations of treatment ranging from 2 to 12 weeks, and includes 462 patients with hypercholesterolemia, with or without additional risk factors for CV disease.
Table 5: Treatment-Emergent Adverse Events Reported in 5% or More of Patients in Studies that
Evaluated Lomitapide Monotherapy in the Non-HoFH Study Pool (Safety Population)
| PREFERRED TERM | LOMITAPIDE MONOTHERAPY (N=291) N (%) | PLACEBO (N=116) N (%) | ACTIVE CONTROL (N=55) N (%) |
| Diarrhea | 163 (56.0) | 13 (11.2) | 4 (7.3) |
| Nausea | 68 (23.4) | 4 (3.4) | 3 (5.5) |
| Flatulence | 32 (11.0) | 7 (6.0) | 0 |
| Headache | 27 (9.3) | 13 (11.2) | 2 (3.6) |
| Abdominal Pain Upper | 25 (8.6) | 4 (3.4) | 0 |
| Abdominal Distension | 24 (8.2) | 4 (3.4) | 3 (5.5) |
| Abdominal Pain | 23 (7.9) | 2 (1.7) | 2 (3.6) |
| Alanine Aminotransferase Increased | 22 (7.6) | 1 (0.9) | 1 (1.8) |
| Fatigue | 21 (7.2) | 3 (2.6) | 0 |
| Vomiting | 20 (6.9) | 3 (2.6) | 0 |
| Aspartate Aminotransferase Increased | 19 (6.5) | 1 (0.9) | 1 (1.8) |
| Dyspepsia | 15 (5.2) | 3 (2.6) | 4 (7.3) |
| Back Pain | 11 (3.8) | 6 (5.2) | 2 (3.6) |
| Nasopharyngitis | 5 (1.7) | 6 (5.2) | 4 (7.3) |
8.3 Less Common Clinical Trial Adverse Reactions
Less common adverse events reported following treatment with lomitapide include the following, without attribution of causality:
Blood and lymphatic system disorders: anemia
Cardiovascular: myocardial infarction (1 case), chest pain
Ear and labyrinth disorders: vertigo
Eye disorders: eye swelling
Gastrointestinal disorders: dry mouth, eructation, gastroesophageal reflux, abdominal or epigastric discomfort, hematemesis, lower gastrointestinal hemorrhage, reflux esophagitis
General Disorders and administrative site conditions: asthenia, chills, early satiety, gait disturbance, malaise, pyrexia, anxiety, hypersensitivity
Hepatobiliary disorders: hepatomegaly
Infections: gastroenteritis, influenza, nasopharyngitis, sinusitis
Laboratory Investigations: blood bilirubin increased, gamma-glutamyltransferase increased, neutrophil percentage increased, protein urine, prothrombin time (INR) prolonged, pulmonary function test abnormal, white blood cell count increased.
Metabolism and nutrition disorders: dehydration, increased or decreased appetite, decreased weight
Musculoskeletal and connective tissue disorders: arthralgia, myalgia, pain in extremity, joint swelling, muscle twitching
Nervous system disorders: paresthesia, dizziness, somnolence, transient ischemic attack (1 case)
Renal and urinary disorders: hematuria
Respiratory, thoracic and mediastinal disorders: pharyngeal lesion, cough
Skin and subcutaneous tissue disorders: hyperhidrosis, rash, pruritus
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data
Clinical Trial Findings
A thorough review of hematology, renal function, electrolytes, serum protein and creatine phosphokinase, did not reveal any effect of lomitapide on these parameters.
Hepatic Transaminase Elevations
During the HoFH pivotal registration trial, 10 of 29 (34%) patients had at least one elevation in ALT and/or AST ≥3x ULN, see Table 6. No clinically meaningful elevations in total bilirubin or alkaline phosphatase were observed. Transaminases typically fell within one to four weeks of reducing the dose or stopping JUXTAPID.
There was no consistent dose-response relationship that predicted onset of liver enzyme elevation. Among the 10 patients with elevations ≥3x ULN, the dose of JUXTAPID at the time of the initial maximum elevation in transaminase levels was 10 mg in 3 patients, 20 mg in 1 patient, 40 mg in 4 patients, and 60 mg in 2 patients. Decreasing or interrupting the dose of JUXTAPID resulted in predictable reductions in hepatic aminotransferase levels.
Table 6: Highest Liver Function Test Results Post First Dose in HoFH Patients
| N (%) | |
| Total Patients | 29 |
| Maximum ALT | |
| ≥3 to <5 x ULN | 6 (21%) |
| ≥5 to <10 x ULN | 3 (10%) |
| ≥10 to <20 x ULN | 1 (3%) |
| ≥20x ULN | 0 |
| Maximum AST | |
| ≥3 to <5 x ULN | 5 (17%) |
| ≥5 to <10 x ULN | 1 (3%) |
| ≥10 to <20 x ULN | 0 |
| ≥20x ULN | 0 |
Among the 19 patients who enrolled in an extension study following the HoFH pivotal registration trial, one discontinued because of increased transaminases that persisted despite several dose reductions, and one temporarily discontinued because of markedly elevated transaminases (ALT 24x ULN, AST 13x ULN) that had several possible causes, including a drug interaction between JUXTAPID, and the strong CYP 3A4 inhibitor, clarithromycin.
Hepatic Steatosis
Hepatic fat was prospectively measured using magnetic resonance spectroscopy (MRS) in all eligible patients during the pivotal registration HoFH trial. Table 7 presents maximum changes in hepatic fat from baseline. Mean hepatic fat content was 1% at baseline. After 26 weeks, the median absolute increase in hepatic fat from baseline was 6%, and the mean absolute increase was 8% (range, 0% to 30%). After 78 weeks, the median absolute increase in hepatic fat from baseline was 6%, and the mean absolute increase was 7% (range, 0% to 18%). Among the 23 patients with evaluable data on at least one occasion during the trial, 18 (78%) exhibited an increase in hepatic fat >5%, and 3 (13%) exhibited an increase >20%. Data from individuals who had repeat measurements after stopping JUXTAPID show that hepatic fat accumulation is reversible, but whether histological sequelae remain is unknown.
Table 7: Maximum Categorical Changes in % Hepatic Fat
| MAXIMUM ABSOLUTE INCREASE IN % HEPATIC FAT | EFFICACY PHASE WEEKS 0-26 N (%) | SAFETY PHASE WEEKS 26-78 N (%) | ENTIRE TRIAL WEEKS 0-78 N (%) |
| Number of evaluable patients | 22 | 22 | 23 |
| ≤5% | 9 (41) | 6 (27) | 5 (22) |
| >5% to ≤10% | 6 (27) | 8 (36) | 8 (35) |
| >10% to ≤15% | 4 (18) | 3 (14) | 4 (17) |
| >15% to ≤20% | 1 (5) | 4 (18) | 3 (13) |
| >20% to ≤25% | 1 (5) | 0 | 1 (4) |
| >25% | 1 (5) | 1 (5) | 2 (9) |
8.5 Post-Market Adverse Reactions
The following adverse reaction has been identified during post-approval use of JUXTAPID. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to JUXTAPID exposure.
Skin reactions: Alopecia
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
- JUXTAPID is contraindicated with concomitant administration of >20 mg daily simvastatin (40 mg daily is allowed for patients who have previously tolerated simvastatin 80 mg daily for at least one year without evidence of muscle toxicity) (see 9.4 Drug-Drug Interactions).
JUXTAPID is contraindicated with concomitant use of strong or moderate CYP
3A4 inhibitors (see 9.4 Drug-Drug Interactions).
9.2 Drug Interactions Overview
CYP 3A4 is the isozyme primarily responsible for the metabolism of JUXTAPID (lomitapide). Lomitapide does not induce CYP 1A2, 3A4, or 2B6. Lomitapide inhibits CYP 3A4. Lomitapide does not inhibit CYP 1A2, 2B6, 2C9, 2C19, 2D6, or 2E1.
The major metabolites of lomitapide, M1 and M3, do not induce CYP 1A2, 3A4, or 2B6. M1 and M3 do not inhibit CYP 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, or 3A4.
Lomitapide is not a P-gp substrate. Lomitapide inhibits P-gp (see 4.1 Dosing Considerations) but does not inhibit breast cancer resistance protein (BCRP).
9.3 Drug-Behavioural Interactions
JUXTAPID should be used with caution in patients who consume alcohol because of its potential to induce or exacerbate hepatic injury, including steatosis. Limitation of alcohol use is warranted with JUXTAPID treatment, e.g., a limit of no more than one drink daily.
9.4 Drug-Drug Interactions
Effect of Other Drugs on Lomitapide
Concomitant CYP 3A4 inhibitor use increases lomitapide exposure. Lomitapide exposure increased 27-fold in the presence of ketoconazole, a strong CYP 3A4 inhibitor. Thus, concomitant use of strong CYP 3A4 inhibitors and lomitapide is contraindicated. The effect of moderate CYP 3A4 inhibitors on lomitapide exposure has not been studied. However, moderate CYP 3A4 inhibitors would be expected to increase lomitapide exposure several-fold based on experience with concomitant use of strong and weak CYP 3A4 inhibitors. Thus, concomitant use of moderate CYP 3A4 inhibitors and lomitapide is contraindicated (see 2
CONTRAINDICATIONS).
When lomitapide was co-administered with weak CYP 3A4 inhibitors, e.g., atorvastatin, ethinyl estradiol/norgestimate, increases in lomitapide exposure were noted, see Table 8, below (see 4.1 Dosing Considerations).
Table 8: Established or Potential Drug-Drug-Interactions: Effect of Coadministered Drugs on
Lomitapide Systemic Exposure
| Proper/ Common Name | Source of Evidence | Effect | Clinical Comment |
| Ketoconazole | CT | Co-administration of ketoconazole 200 mg BID with lomitapide 60 mg QD increased lomitapide AUC by 2652% and Cmax by 1355% | Ketoconazole is contraindicated with lomitapide (see 2 CONTRAINDICATIONS, and Concomitant Use of CYP 3A4 inhibitors) |
| Atorvastatin | CT | Simultaneous dosing of atorvastatin 80 mg QD and lomitapide 20 mg QD increased lomitapide AUC by 94%and Cmax 128% Dosing atorvastatin 80 mg QD and lomitapide 20 mg QD separated by 12 hours, increased lomitapide AUC by 24% and Cmax by 21% | JUXTAPID should either be taken separately, i.e., 12 hours apart, or the dose of JUXTAPID should be reduced by 50%. (see 4.1 Dosing Considerations) |
| Proper/ Common Name | Source of Evidence | Effect | Clinical Comment |
Ethinyl Estradiol/norgestimate | CT | Simultaneous dosing of ethinyl estradiol 0.035 mg / norgestimate 0.25 mg QD and lomitapide 20 mg QD increased lomitapide AUC by 34% and Cmax by 44% Dosing ethinyl estradiol 0.035 mg / norgestimate 0.25 mg QD and lomitapide 20 mg QD separated by 12 hours increased lomitapide AUC by 25% and Cmax by 34% | JUXTAPID should either be taken separately, i.e., 12 hours apart, or the dose of JUXTAPID should be reduced by 50%. (see 4.1 Dosing Considerations) |
BID = twice daily; CT = clinical trial; QD = once daily
Effect of Lomitapide on Other Drugs
Table 9 summarizes the effects of lomitapide on the AUC and Cmax of coadministered drugs.
Table 9: Established or Potential Drug-Drug Interactions: Effect of Lomitapide on the Systemic
Exposure of Coadministered Drugs
| Proper/ Common Name | Source of Evidence | Effect | Clinical Comment |
| Simvastatin | CT | Co-administration of lomitapide 60 mg QD for 7 days with simvastatin 40 mg single dose increased simvastatin AUC by 99% and Cmax by 102% and increased simvastatin acid AUC by 71% and Cmax by 57% Co-administration of lomitapide 10 mg QD for 7 days with simvastatin 40 mg single dose increased simvastatin AUC by 62% and Cmax by 65% and increased simvastatin acid AUC by 39% and Cmax by 35%. | Limit simvastatin dosage to 20 mg daily (or 40 mg daily for patients who have previously tolerated simvastatin 80 mg daily for at least one year without evidence of muscle toxicity). Refer to the simvastatin prescribing information for additional dosing recommendations. |
| Warfarin | CT | Co-administration of lomitapide 60 mg QD for 12 days with warfarin 10 mg single dose increased R(+) warfarin AUC by 28% and Cmax by 14%, increased S(-)warfarin AUC by 30% and Cmax by 15% and increased INR AUC by 7% and Cmax by 22%. | Patients taking warfarin should undergo more frequent monitoring of the INR, especially after any changes in lomitapide dosage (see 4.1 Dosing Considerations). |
| Proper/ Common Name | Source of Evidence | Effect | Clinical Comment |
| Atorvastatin | CT | Co-administration of lomitapide 60 mg QD for 7 days with atorvastatin 20 mg single dose increased atorvastatin acid AUC by 52% and Cmax by 63%. Co-administration of lomitapide 10 mg QD for 7 days with atorvastatin 20 mg single dose increased atorvastatin acid AUC by 11% and Cmax by 19%. | No dosing adjustments may be required for atorvastatin. |
| Rosuvastatin | CT | Co-administration of lomitapide 60 mg QD for 7 days with rosuvastatin 20 mg single dose increased rosuvastatin AUC by 32% and Cmax by 4%. Co-administration of lomitapide 10 mg QD for 7 days with rosuvastatin 20 mg single dose increased rosuvastatin AUC by 2% and Cmax by 6%. | No dosing adjustments may be required for rosuvastatin. |
| Fenofibrate, micronized | CT | Co-administration of lomitapide 10 mg QD for 7 days with fenofibrate, micronized 145 mg single dose decreased fenofibric acid AUC by 10% and Cmax by 29%. | No dosing adjustments may be required for fenofibrate, micronized. |
| Ezetimibe | CT | Co-administration of lomitapide 10 mg QD for 7 days with ezetimibe10 mg single dose increased total ezetimibe AUC by 6% and Cmax by 3%. | No dosing adjustments may be required for ezetimibe. |
| Extended-release niacin | CT | Co-administration of lomitapide 10 mg QD for 7 days with extended-release niacin 1000 mg single dose increased nicotinic acid AUC by 10% and Cmax by 11% and decreased nicotinuric acid AUC by 21% and Cmax by 15%. | No dosing adjustments may be required for extended-release niacin. |
| Ethinyl estradiol | CT | Co-administration of lomitapide 50 mg QD for 8 days with ethinyl estradiol 0.035 mg QD for 28 days decreased ethinyl estradiol AUC by 8% and Cmax by 8%. | No dosing adjustments may be required for ethinyl estradiol. |
| Norgestimate | CT | Co-administration of lomitapide 50 mg QD for 8 days with norgestimate 0.25 mg QD for 28 days increased total 17-deacetyl norgestimate AUC by 6% and Cmax by 2%. | No dosing adjustments may be required for norgestimate. |
CT = clinical trial; QD = once daily; INR = international normalized ratio
9.5 Drug-Food Interactions
Since grapefruit juice is a moderately strong inhibitor of CYP 3A4, patients taking JUXTAPID should avoid consumption of grapefruit juice (see 4.1 Dosing Considerations). 9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
JUXTAPID (lomitapide) is a potent, selective inhibitor of microsomal triglyceride transfer protein (MTP), an intracellular lipid-transfer protein that is found in the lumen of the endoplasmic reticulum and is responsible for binding and shuttling individual lipid molecules between membranes. MTP plays a key role in the assembly of apo B containing lipoproteins in the liver and intestines. Inhibition of MTP impairs the synthesis of chylomicrons and VLDL. The inhibition of the synthesis of VLDL leads to reduced levels of plasma LDL-C. Lomitapide has a mechanism of action that differs from those of other classes of lipid lowering agents (e.g., statins, bile acid sequestrants, cholesterol absorption inhibitors). This distinct mechanism appears to be complementary to that of other lipid-lowering agents, as listed just above.
10.2 Pharmacodynamics
QT Study
At a concentration of 23 times the Cmax of the maximum recommended dose of lomitapide, no clinically relevant prolongation of QTc was observed.
10.3 Pharmacokinetics
Absorption:
Upon oral administration of a single 60-mg dose of lomitapide, its Tmax is around 6 (4-8) hours in healthy volunteers. The absolute bioavailability of lomitapide is approximately 7%, limited primarily by an extensive first-pass effect. Lomitapide pharmacokinetics is approximately dose-proportional for oral single doses from 10-100 mg.
Lomitapide Cmax and AUC were increased following a high-fat meal (77% and 58%, respectively), or a low-fat meal (70% and 28%, respectively).
Distribution:
The mean lomitapide volume of distribution at steady-state is 985-1,292 L. Lomitapide is 99.8% plasma-protein bound.
Metabolism:
Lomitapide is metabolized extensively by the liver. The metabolic pathways include oxidation, oxidative N-dealkylation, glucuronide conjugation, and piperidine ring opening. Cytochrome P450 (CYP) 3A4 metabolizes lomitapide to its major metabolites, M1 and M3, as detected in plasma. The oxidative N-dealkylation pathway breaks the lomitapide molecule into M1 and M3. M1 is the moiety that retains the piperidine ring, whereas M3 retains the rest of the lomitapide molecule in vitro. CYP 1A2, 2B6, 2C8, and 2C19 may metabolize lomitapide to a small extent to M1. M1 and M3 do not inhibit activity of microsomal triglyceride transfer protein in vitro.
Elimination:
In a mass-balance study, a mean of 59.5% and 33.4% of the dose was excreted in the urine and feces, respectively. In another mass-balance study, a mean of 52.9% and 35.1% of the dose was excreted in the urine and feces, respectively. Lomitapide itself was not detectable in urine samples. M1 is the major urinary metabolite. Lomitapide is the major component in the feces. The mean lomitapide terminal half-life is 39.7 hours.
Special Populations and Conditions
Sex: There was no clinically relevant effect of gender on the pharmacokinetics of
JUXTAPID.
- Ethnic Origin: No dose adjustment is required for Caucasian or Latino patients. There is insufficient information to determine if JUXTAPID requires dose adjustment in other races. However, since JUXTAPID is dosed in an escalating fashion according to individual patient response, no adjustment to the dosing regimen is recommended for JUXTAPID administration based on race.
- Hepatic Insufficiency: A single-dose, open-label study was conducted to evaluate the pharmacokinetics of 60 mg lomitapide in healthy volunteers with normal hepatic function compared with patients with mild (Child-Pugh A) and moderate (Child-Pugh B) hepatic impairment. In patients with moderate hepatic impairment, lomitapide AUC and Cmax were 164% and 361% higher, respectively, compared with healthy volunteers. In patients with mild hepatic impairment, lomitapide AUC and Cmax were 47% and 4% higher, respectively, compared with healthy volunteers. Lomitapide has not been studied in patients with severe hepatic impairment (Child-Pugh score 10-15).
- Renal Insufficiency A single-dose, open-label study was conducted to evaluate the pharmacokinetics of 60 mg lomitapide in patients with end-stage renal disease receiving hemodialysis compared with healthy volunteers with normal renal function. Healthy volunteers had estimated creatinine clearance >80 mL/min by the Cockcroft-Gault equation. Compared with healthy volunteers, lomitapide AUC0-inf and Cmax were 40% and 50% higher, respectively, in patients with end-stage renal disease receiving hemodialysis. Effects of mild, moderate, and severe renal impairment as well as end-stage renal disease not yet on dialysis on lomitapide exposure have not been studied.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15°C to 30°C. Keep container tightly closed and protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: lomitapide mesylate
Chemical name: N-(2,2,2-trifluoroethyl)-9-[4-[4-[[[4'-(trifluoromethyl)[1,1'-biphenyl]-2-yl]carbonyl]amino]-1-piperidinyl]butyl]-9H-fluorene-9-carboxamide, methanesulfonate salt
Molecular formula and molecular mass: C39H37F6N3O2 ● CH4O3S
Molecular mass of lomitapide mesylate: 789.8 g/mol
Molecular mass of lomitapide (free base): 693.7 g/mol
Structural formula:
Physicochemical properties: Lomitapide mesylate is a white to off-white powder that is slightly soluble in aqueous solutions of pH 2 to 5. Lomitapide mesylate is freely soluble in acetone, ethanol and methanol; soluble in 2-butanol, methylene chloride and acetonitrile; sparingly soluble in 1-octanol and 2-propanol; slightly soluble in ethyl acetate; and insoluble in heptane.
Each JUXTAPID capsule contains lomitapide mesylate equivalent to 5, 10 or 20 mg lomitapide free base and the following inactive ingredients: pregelatinized starch, sodium starch glycolate, microcrystalline cellulose, lactose monohydrate, silicon dioxide and magnesium stearate. The capsule shells contain gelatin and titanium dioxide. In addition, the orange capsule shells contain red iron oxide. The imprinting ink contains shellac, black iron oxide and propylene glycol. 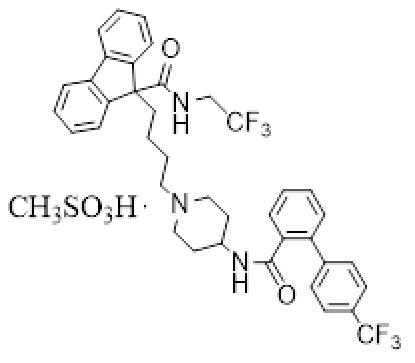
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
HoFH
Table 10: Summary of patient demographics for clinical trials in HoFH
| Study # | Study design | Dosage, route of | Study subjects (n) | Mean age (Range) | Sex | ||
| administration | |||||||
| and duration | |||||||
| UP1002/ AEGR-733-005 | Phase 3, non- randomized, single group assignment | 5 mg daily titrated to 10 mg, 20mg, 40 mg and 60mg as tolerated; Oral; 52 weeks | N=29 | 30.7 years (18-55) | Male=16 (55.2%) | ||
The safety and effectiveness of JUXTAPID as an adjunct to a low-fat diet and other lipid-lowering treatments at optimized doses, including LDL apheresis where available, were evaluated in a multinational, single-arm, open-label, pivotal registration trial involving 29 adults with HoFH. A diagnosis of HoFH was defined by the presence of at least one of the following clinical criteria: (1) documented functional mutation(s) in both LDL receptor alleles or alleles known to affect LDL receptor functionality, or (2) skin fibroblast LDL receptor activity <20% normal, or (3) untreated TC >500 mg/dL and TG <300 mg/dL and both parents with documented untreated TC >250 mg/dL.
Among the 29 patients enrolled, the mean age was 30.7 years (range, 18 to 55 years), 16 (55%) were men, and the majority (86%) were Caucasian. The mean body mass index (BMI) was 25.8 kg/m2, with four patients meeting BMI criteria for obesity; one patient had type 2 diabetes. Concomitant lipid-lowering treatments at baseline included one or more of the following: statins (93%), ezetimibe (76%), nicotinic acid (10%), bile acid sequestrant (3%), and fibrate (3%); 18 (62%) were receiving apheresis.
After a six-week run-in period to stabilize lipid-lowering treatments, including the establishment of an LDL apheresis schedule if applicable, JUXTAPID was initiated at 5 mg daily and titrated to daily doses of 10 mg, 20 mg, 40 mg, and 60 mg at weeks 2, 6, 10, and 14, respectively, based on tolerability and acceptable levels of transaminases. Patients were instructed to maintain a low-fat diet (<20% calories from fat) and to take dietary supplements that provided approximately 400 international units vitamin E, 210 mg alpha-linolenic acid (ALA), 200 mg linoleic acid, 110 mg eicosapentaenoic acid (EPA), and 80 mg docosahexaenoic acid (DHA) per day. After efficacy was assessed at Week 26, patients remained on JUXTAPID for an additional 52 weeks to assess long-term safety. During this safety phase, the dose of JUXTAPID was not increased above each patient’s maximum tolerated dose established during the efficacy phase, but changes to concomitant lipid-lowering treatments were allowed.
Twenty-three (79%) patients completed the efficacy endpoint at Week 26, all of whom went on to complete 78 weeks of treatment. Adverse events contributed to premature discontinuation for five patients. The maximum tolerated doses during the efficacy period were 5 mg (10%), 10 mg (7%), 20 mg (21%), 40 mg (24%), and 60 mg (34%).
Phase 2 Study UP1001
The demographic characteristics of the HoFH population were similar in the Phase 2 (UP1001) and pivotal registration (Study UP1002/AEGR-733-005) studies (Table 11).
All 35 patients met the protocol-defined HoFH diagnostic criteria. Mean Baseline LDL-C for the 6 patients in the Phase 2 study was markedly elevated at 614.2 mg/dL (15.9 mmol/L) as these patients were required to be off all LLT within 4 weeks of study entry. In the pivotal registration study, where patients were required to be on a stable regimen of their LLT, mean Baseline LDL-C was also elevated at 336.0 mg/dL (8.7 mmol/L) despite their use of standard of care therapies.
Table 11: Demographics and Baseline Characteristics, HoFH Study Pool (Full Analysis Set)
| CHARACTERISTIC | STUDY UP1001 (N=6) | STUDY UP1002/ 733-005 (N=29) |
| Age (years) | ||
| Mean (SD) | 25.0 (9.19) | 30.7 (10.56) |
| Minimum, Maximum | 17, 39 | 18, 55 |
| Number (%) Male | 3 (50.0) | 16 (55.2) |
| Number (%) Caucasian | 3 (50.0) | 25 (86.2) |
| BMI (kg/m2), n (%) | ||
| <30 | 5 (83.3) | 25 (86.2) |
| ≥30 | 1 (16.7) | 4 (13.8) |
| Baseline LDL-C (mg/dL) | ||
| Mean (SD) | 614.2 (105.85)1 | 336.0 (113.75) |
| Minimum, Maximum | 480, 789 | 152, 565 |
| Baseline LDL-C (mmol/L) | ||
| Mean (SD) | 15.9 (2.74)1 | 8.7 (2.94) |
| Minimum, Maximum | 12, 20 | 4, 15 |
1 Subjects were required to be off all LLTs within 4 weeks of study entry.
Overall, 27 (93%) of the 29 patients in the pivotal registration study were on optimized doses of HMG-CoA reductase inhibitors (statins) at study entry, primarily rosuvastatin (45%) and atorvastatin (31%); 17% of patients were receiving simvastatin. A total of 76% of patients were receiving ezetimibe, all coadministered with a statin; 10% were on niacin and 3% were on a bile acid sequestrant. Eighteen (62%) of the 29 patients were receiving apheresis at baseline in the pivotal registration study. As detailed in Table 11, all 6 patients in the Phase 2 study were required to be off all other LLT.
The effects of JUXTAPID (lomitapide) on LDL-C, TC, apo B, TG, and HDL-C, when added to a low-fat diet and other lipid-lowering therapies in patients with homozygous familial hypercholesterolemia (HoFH) are presented in Table 12, below.
The primary efficacy endpoint was percent change in LDL-C from baseline to Week 26. At Week 26, the mean and median percent changes in LDL-C from baseline were 40% (paired t-test p<0.001) and 50%, respectively, based on the intent-to-treat population with last observation carried forward (LOCF) for patients who discontinued prematurely. The mean percent change in LDL-C from baseline through Week 26 is shown in Figure 1 for the 23 patients who completed the efficacy period.
Figure 1: Mean Percent Changes in LDL-C in the HoFH Pivotal Registration Study, from Baseline
(Week 26 Completers)
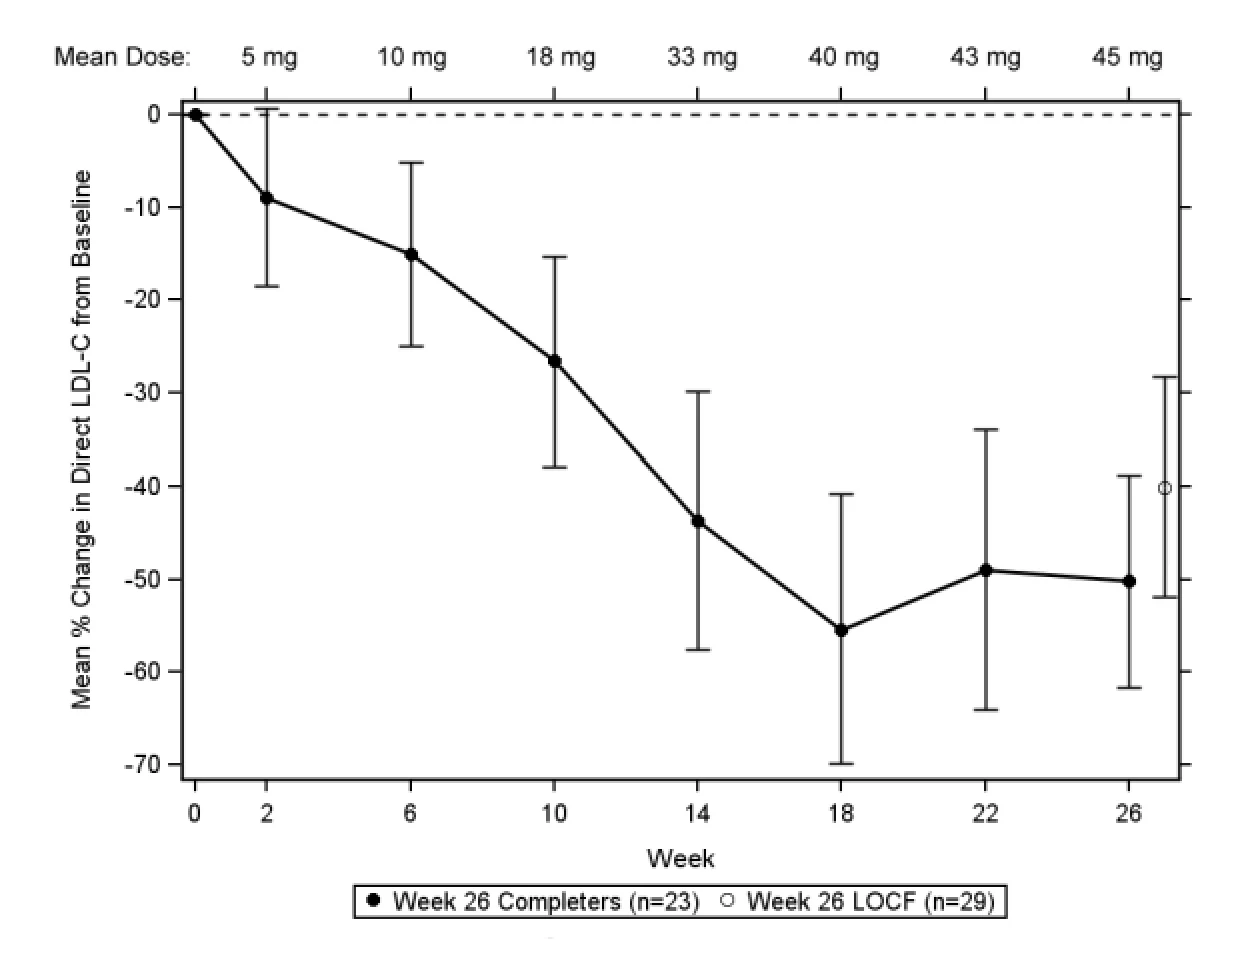
Error bars represent 95% confidence intervals of the mean.
Changes in lipids and lipoproteins through Week 26 and Week 56 of JUXTAPID treatment are presented in Table 12.
Table 12: Absolute Values and Percent Changes from Baseline to Weeks 26 and 56 in Lipids and Lipoproteins in HoFH Patients
| PARAMETER | UNITS | BASELINE | WEEK 26/LOCF (N=29) | WEEK 56 (N=23) | ||||
| Mean (SD) | Mean (SD) | % Changeb | p- valuec | Mean (SD) | % Changeb | p-valuec | ||
| LDL-C, direct | mg/dL | 336 (114) | 190 (104) | -40 | <0.001 | 199 (123) | -44 | <0.001 |
| mmol/L | 8.7 (3.0) | 4.9 (2.7) | 5.2 (3.2) | |||||
| TC | mg/dL | 430 (135) | 258 (118) | -36 | <0.001 | 274 (144) | -39 | <0.001 |
| mmol/L | 11.1 (3.5) | 6.7 (3.1) | 7.1 (3.7) | |||||
| apo B | mg/dL | 259 (80) | 148 (74) | -39 | <0.001 | 149 (83) | -45 | <0.001 |
| mmol/L | 6.7 (2.1) | 3.8 (1.9) | 3.9 (2.1) | |||||
| TGa | mg/dL | 92 | 57 | -45 | 0.009 | 61 | -33 | 0.004 |
| mmol/L | 1.0 | 0.6 | 0.7 | |||||
| Non-HDL-C | mg/dL | 386 (132) | 217 (113) | -40 | <0.001 | 229 (139) | -44 | <0.001 |
| mmol/L | 10.0 (3.4) | 5.6 (2.9) | 5.9 (3.6) | |||||
| VLDL-C | mg/dL | 21 (10) | 13 (9) | -29 | 0.012 | 16 (14) | -28 | 0.005 |
| mmol/L | 0.5 (0.3) | 0.3 (0.2) | 0.4 (0.4) | |||||
| Lp(a)a | nmol/L | 66 | 61 | -13 | 0.094 | 56 | -21 | <0.001 |
| HDL-C | mg/dL | 44 (11) | 41 (13) | -7 | 0.072 | 45 (15) | +1 | 0.920 |
| mmol/L | 1.1 (0.3) | 1.1 (0.3) | 1.2 (0.4) | |||||
a Median presented for TG and Lp(a). p-value is based on the mean percent change
b The % change values are calculated based on gravimetric units
c p--value on the mean percent change from baseline based on paired t-test
For the 23 of 29 HoFH patients who completed 78 weeks of lomitapide treatment, the mean LDL-C values were 210 mg/dL (5.4 mmol/L), a mean change of 38%. For these patients, the baseline mean LDL-C was 352 mg/dL (9.1 mmol/L).
At baseline, 93% of patients were on a statin; 76% were on ezetimibe; 10% were on niacin; 3% were on a bile acid sequestrant; and 62% were receiving apheresis. Fourteen of 23 (61%) patients had their baseline concomitant lipid-lowering treatment (LLT) reduced by Week 56, including planned and unplanned reductions/interruptions. Apheresis was discontinued in 3 of 13 patients who were on it at Week 26, while its frequency was reduced in 1 patient, while maintaining acceptable LDL-C levels through Week 56 in all four. Of the 23 patients who completed through Week 26, 19 (83%) had LDL-C reductions ≥25%, with 8 (35%) having LDL-C < 100 mg/dL (2.6 mmol/L), and 1 having LDL-C <70 mg/dL (1.8 mmol/L) at that time point.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Carcinogenicity: In a 2-year dietary carcinogenicity study in mice, lomitapide was administered at doses of 0.3, 1.5, 7.5, 15, or 45 mg/kg/day. There were statistically significant increases in the incidences of liver adenomas and carcinomas in males at doses ≥1.5 mg/kg/day (≥2-times the MRHD at 60 mg based on AUC) and in females at ≥7.5 mg/kg/day (≥10-times the human exposure at 60 mg based on AUC). Incidences of small intestinal carcinomas in males and combined adenomas and carcinomas in females were significantly increased at doses ≥15 mg/kg/day (≥23-times the human exposure at 60 mg based on AUC).
In a 2-year carcinogenicity study in rats, lomitapide was administered by oral gavage for up to 99 weeks at doses of 0.25, 1.7, or 7.5 mg/kg/day in males and 0.03, 0.35, or 2.0 mg/kg/day in females. While the design of the study was suboptimal, there were no statistically significant drug-related increases in tumor incidences at exposures up to 6-times (males) and 8-times (females) higher than human exposure at the MRHD based on AUC.
Genotoxicity: Lomitapide did not exhibit genotoxic potential in a battery of studies, including the in vitro Bacterial Reverse Mutation (Ames) assay, an in vitro cytogenetics assay using primary human lymphocytes, and an oral micronucleus study in rats.
Reproductive and Developmental Toxicology: Lomitapide had no effect on fertility in rats at doses up to 5 mg/kg/day at systemic exposures estimated to be 4-times (females) and 5-times (males) higher than in humans at 60 mg based on AUC.