


Product Monograph - Advil Flu
Recent Major Label Changes
2 Contraindications 3 Serious Warnings and Precautions Box 7 Warnings and Precautions; Monitoring and Laboratory Tests – Pregnancy; Special Populations - Pregnancy | Date of revision 2024/10 |
|---|---|
| 7 Warnings and Precautions - Cardiovascular | Date of revision 2026/01 |
Table of Contents
Certain sections or subsections that are not applicable at the time of preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 5
- 1.
Indications .................................................................................................................. 5
Pediatrics .......................................................................................................................... 5
Geriatrics .......................................................................................................................... 5
- 2. Contraindications ........................................................................................................ 5
- 3. Serious Warnings and Precautions Box ....................................................................... 6
- 4.
Dosage and Administration ......................................................................................... 6
Dosing Considerations ...................................................................................................... 6
Recommended Dose and Dosage Adjustment ................................................................. 6
Administration ................................................................................................................. 7
Missed Dose ..................................................................................................................... 7
- 5. Overdose..................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition and Packaging ................................................ 8
- 7.
Warnings and Precautions ........................................................................................... 8
General ............................................................................................................................. 9
Cardiovascular .................................................................................................................. 9
Dependence/Tolerance and/or Abuse Liability ................................................................ 9
Ear/Nose/Throat .............................................................................................................. 9
Endocrine and Metabolism .............................................................................................. 9
Fluid and Electrolyte Balance ........................................................................................... 9
Gastrointestinal .............................................................................................................. 10
Genitourinary ................................................................................................................. 11
Hematologic ................................................................................................................... 11
Hepatic/Biliary/Pancreatic ............................................................................................. 11
Immune .......................................................................................................................... 12
Monitoring and Laboratory Tests ................................................................................... 12
Pregnancy ....................................................................................................................... 12
Neurologic ...................................................................................................................... 12
Ophthalmologic .............................................................................................................. 12
Peri-Operative Considerations ....................................................................................... 12
Psychiatric ...................................................................................................................... 12
Renal .............................................................................................................................. 13
Respiratory ..................................................................................................................... 13
Sensitivity/Resistance ..................................................................................................... 13
Skin ................................................................................................................................. 13
7.1 Special Populations .................................................................................................. 14
7.1.1 Pregnancy ........................................................... Error! Bookmark not defined.
7.1.2 Breastfeeding ................................................................................................. 15
7.1.3 Pediatrics ........................................................................................................ 15
7.1.4 Geriatrics ........................................................................................................ 15
- 8.
Adverse Reactions ..................................................................................................... 16
8.1 Adverse Reaction Overview ...................................................................................... 16
8.2 Clinical Trial Adverse Reactions ................................................................................ 16
8.5 Post-Market Adverse Reactions ............................................................................... 19
- 9.
Drug Interactions ...................................................................................................... 23
9.1 Serious Drug Interactions ......................................................................................... 23
9.2 Drug Interactions Overview ...................................................................................... 23
9.3 Drug-Behaviour Interactions .................................................................................... 23
9.4 Drug-Drug Interactions ............................................................................................. 23
9.5 Drug-Food Interactions ............................................................................................ 27
9.6 Drug-Herb Interactions ............................................................................................. 27
9.7 Drug-Laboratory Test Interactions ........................................................................... 27
- 10. Clinical Pharmacology ............................................................................................... 28
10.1 Mechanism of Action ................................................................................................ 28
10.2 Pharmacodynamics ................................................................................................ 28
10.3 Pharmacokinetics ................................................................................................... 29
- 11. Storage, Stability and Disposal .................................................................................. 31
Part 2: Scientific Information ................................................................................................ 32
- 13. Pharmaceutical Information ...................................................................................... 32
- 14.
Clinical Trials ............................................................................................................. 33
14.1 Clinical Trials by Indication ..................................................................................... 33
- 15. Microbiology ............................................................................................................. 34
- 16. Non-Clinical Toxicology ............................................................................................. 34
Patient Medication Information ........................................................................................... 38
Part 1: Healthcare Professional Information
1. Indications
ADVIL FLU (ibuprofen and diphenhydramine hydrochloride) is indicated for:
- The relief of influenza symptoms including dry cough, sneezing, runny nose, fever, and chills, headache, body aches and pains and sore throat pain.
Pediatrics
Pediatrics (< 16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ADVIL FLU in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. The use of ADVIL FLU in this population should only be recommended after evaluation on an individual basis, by a physician.
2. Contraindications
- patients with active peptic ulcer, a history of recurrent ulceration or active inflammatory disease of the gastrointestinal system.
- patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging. The potential for cross-reactivity between different NSAIDs must be kept in mind.
- patients with the complete or partial syndrome of nasal polyps, or in whom asthma, anaphylaxis, urticaria/angioedema, rhinitis or other allergic manifestations are precipitated by ASA or other nonsteroidal anti-inflammatory agents. Fatal anaphylactoid reactions have occurred in such individuals. As well, individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse effects.
- significant hepatic impairment or active liver disease.
- severely impaired or deteriorating renal function (creatinine clearance <30 mL/min). Individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored.
- coadministration with other NSAIDs because of the absence of any evidence demonstrating synergistic benefits and the potential for additive side effects.
- children with kidney disease and children who have suffered significant fluid loss due to vomiting, diarrhea or lack of fluid intake, should not be given ibuprofen.
- patients with systemic lupus erythematosus, as an anaphylaxis-like reaction with fever may occur, particularly when ibuprofen has been administered previously.
- Ibuprofen should not be used during the third trimester of pregnancy because of risk of premature closure of the ductus arteriosus, and prolonged parturition.
- administration right before or after heart surgery.
- the presence of known hyperkalemia (see 7 Warnings and Precautions - Renal).
- children and adolescents (see 1 Indications).
3. Serious Warnings and Precautions Box
- Causes sedation or sleepiness.
- Use with caution in patients prone to gastrointestinal tract irritation, including those with a history of peptic ulcer (see 7 Warnings and Precautions - Gastrointestinal and 9 Drug Interactions - Coumarin-type Anticoagulants).
- Use with caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention (see 7 Warnings and Precautions - Cardiovascular and 7 Warnings and Precautions - Fluid and Electrolyte Balance and 9 Drug Interactions - Antihypertensives).
- Patients at greatest risk of renal toxicity are those with impaired renal function, heart failure, liver dysfunction, those taking diuretics and the elderly (see 7 Warnings and Precautions - Renal).
- If urinary symptoms, hematuria and cystitis occur, the drug should be stopped immediately (see 7 Warnings and Precautions - Genitourinary).
- Ibuprofen is contraindicated for use during the third trimester of pregnancy because of risk of premature closure of the ductus arteriosus and uterine inertia (prolonged parturition) (see 2 Contraindications)
- Caution should be exercised in prescribing Advil products if trying to conceive, during the first and second trimesters of pregnancy or breastfeeding. Use of NSAIDS at approximately 20 weeks of gestation or later may cause oligohydramnios, and renal dysfunction including renal failure (see 7 Warnings and Precautions - Pregnancy and 7 Warnings and Precautions - Breastfeeding).
4. Dosage and Administration
Dosing Considerations
- Do not take longer than 2 days for sore throat pain, 3 days for fever or 5 days for pain and flu symptoms unless directed by a physician.
- Patients older than 65 years should not use these products.
- The lowest effective dose should be used for the shortest possible duration.
Recommended Dose and Dosage Adjustment
Adults 16 to 65 years: Take 1 (every 4 hours) or 2 (every 6 to 8 hours) Liqui-Gel capsules as needed.
- Do not exceed 6 Liqui-Gel capsules in 24 hours unless directed by a physician.
- ADVIL FLU can be taken 4-6 hours after the last ibuprofen and/or diphenhydramine dose.
- Health Canada has not authorized an indication for pediatric use in children under 16 years of age.
Administration
- See 4.2 Recommended Dose and Dosage Adjustment
Missed Dose
- Do not take twice the recommended dose after a missed dose.
5. Overdose
Symptoms of Overdosage
ADVIL FLU contains ibuprofen and diphenhydramine hydrochloride. The toxicity of overdose is dependent upon the amount of drug ingested and the time elapsed since ingestion; individual responses may vary, thus making it necessary to evaluate each case separately.
Although uncommon, serious toxicity and death have been reported with ibuprofen overdosage. The most frequently reported symptoms of ibuprofen overdose include abdominal pain, nausea, vomiting, lethargy and drowsiness. Other CNS symptoms include headache, tinnitus, CNS depression and seizures. Metabolic acidosis, coma, acute renal failure and apnoea (primarily in very young pediatric patients), hyperkalaemia, and respiratory depression may rarely occur. Cardiovascular toxicity, including hypotension, bradycardia, tachycardia and atrial fibrillation, have also been reported.
Signs and symptoms of diphenhydramine overdose are anticholinergic in nature and can include dry mucous membranes, decreased bowel sounds, mydriasis, flushed skin, hyperthermia, drowsiness, tachycardia, urinary retention, coma, hallucinations and seizures. Death has resulted from seizures and/or cardiac arrhythmias. Cardiac arrhythmias are similar to those following an overdose of other drugs and class Ia antiarrhythmic properties and result from the blockade of fast sodium channels.
Treatment of Overdosage
In cases of acute overdose, the stomach should be emptied through induction of emesis (in alert patients only) or gastric lavage. Due to the rapid absorption of ibuprofen from the gut, emesis is most effective if initiated within 30 minutes of ingestion. Orally administered activated charcoal may help in reducing the absorption of the drugs when given less than 2 hours following ingestion. There is some evidence that repeated administration of activated charcoal may bind the medication that has diffused from the circulation. Inducing diuresis may be helpful. The treatment of acute overdose is primarily supportive. Management of hypotension, acidosis and GI bleeding may be necessary.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Examples of Ibuprofen Overdose
A 41-year-old man with multiple medical problems, including long-term renal insufficiency, developed near-fatal acute renal failure after ingestion of a massive dose (36 g) of ibuprofen. He required dialysis for several months, at which point his renal function improved.
With electrolyte replacement and other intensive measures, a 21-month-old child recovered within 5 days after accidental ingestion of 8 g of ibuprofen. A 2-year-old child who ingested approximately 8 g of ibuprofen was treated with activated charcoal, developed metabolic acidosis and acute renal insufficiency, and recovered within 72 hours. A 6-year-old child became comatose after ingesting 6 g of ibuprofen. He was treated with gastric lavage, charcoal, and various supportive measures and recovered within 24 hours.
Examples of Diphenhydramine Hydrochloride Overdose
In adults, ingestion of 25 mg/kg diphenhydramine hydrochloride was fatal.
In patients six years of age and older, doses as low as 300 mg diphenhydramine have caused moderate toxicity (hallucinations) while doses of 1000 mg or more have been documented to cause severe toxicity (delirium/psychosis, seizures, coma) or death. Rhabdomyolysis has occurred in the absence of severe toxicity.
In one case report, a dose of 25 mg in a 26-year-old man resulted in agitation, confusion and paranoia; the reaction recurred when 50 mg was taken the following night. He had no underlying medical or psychiatric conditions; the only other medication taken was acetaminophen.
6. Dosage Forms, Strengths, Composition and Packaging
Table – Dosage Forms, Strengths, Composition and Packaging
The liqui-gels are available in blister packages of 18 and 36.
7. Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box.
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients |
| Oral | Liqui-gel capsule: ibuprofen 200mg (as free acid and potassium salt) diphenhydramine hydrochloride 25 mg per capsule | Coconut oil, D&C red no. 33, FD&C blue no. 1, gelatin, pharmaceutical ink, polyethylene glycol, potassium hydroxide, purified water, sorbitan, sorbitol. |
General
To minimize the potential risk for an adverse event, the lowest effective dose should be used for the shortest possible duration.
As with other anti-inflammatory drugs, ibuprofen may mask the usual signs of infection.
Ibuprofen is NOT recommended for use with other NSAIDs because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions(see 9 Drug Interactions - Acetylsalicylic acid (ASA) or other NSAIDs)
Patients with epilepsy or seizure disorders, myasthenia gravis, glaucoma, chronic lung disease (emphysema or chronic bronchitis), or difficulty in urination due to prostate enlargement or bladder neck problems should not take this product unless directed by a physician.
If symptoms of fever and pain associated with flu symptoms do not improve within 5 days, patients should stop use and consult a physician.
In case of an overdose, medical help or a poison control centre should be contacted immediately. Prompt medical attention is critical, even in the absence of signs or symptoms.
Cardiovascular
Ibuprofen: Congestive heart failure in patients with marginal cardiac function, elevated blood pressure, peripheral arterial disease and palpitations.
Clinical trial and epidemiological data suggest that the use of ibuprofen, particularly at high doses (2,400 mg daily) and in long-term treatment may be associated with a small increased risk of arterial thrombotic events (for e.g., myocardial infarction or stroke). Overall, epidemiological studies do not suggest that low dose ibuprofen (e.g., ≤ 1,200 mg daily) is associated with an increased risk of myocardial infarction.
Long term continuous use may increase the risk of heart attack or stroke.
Diphenhydramine: Vasoconstrictive effects have been noted.
Dependence/Tolerance and/or Abuse Liability
A combination of butorphanol and diphenhydramine is being increasingly used as a drug of abuse. Diphenhydramine dependence has been documented in case reports involving mentally ill patients.
Ear/Nose/Throat
Patients with complete or partial syndrome of nasal polyps should not use this drug. (See 2 Contraindications)
Endocrine and Metabolism
Patients with thyroid disease should not take this drug unless directed by a physician.
Fluid and Electrolyte Balance
Fluid retention and oedema have been observed in patients treated with ibuprofen. Therefore, as with many other NSAIDs, the possibility of precipitating congestive heart failure in elderly patients or those with compromised cardiac function should be borne in mind. ADVIL FLU should be used with caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention.
With nonsteroidal anti-inflammatory treatment there is a potential risk of hyperkalemia, particularly in patients with conditions such as diabetes mellitus or renal failure; elderly patients; or in patients receiving concomitant therapy with B-adrenergic blockers, angiotensin converting enzyme inhibitors or some diuretics. Serum electrolytes should be monitored periodically during long-term therapy, especially in those patients who are at risk.
Gastrointestinal
Serious gastrointestinal (GI) toxicity, such as peptic ulceration, perforation and gastrointestinal bleeding, sometimes severe and occasionally fatal, can occur at any time, with or without symptoms in patients treated with NSAIDs including ibuprofen.
Minor upper GI problems, such as dyspepsia, are common, usually developing early in therapy. Physicians should remain alert for ulceration and bleeding in patients treated with NSAIDs, even in the absence of previous GI tract symptoms.
In patients observed in clinical trials of such agents, symptomatic upper GI ulcers, gross bleeding, or perforation appear to occur in approximately 1% of patients treated for 3-6 months and in about 2-4% of patients treated for one year. The risk continues beyond one year and possibly increases. The incidence of these complications increases with increasing dose.
ADVIL FLU should be given under close medical supervision to patients prone to GI tract irritation, particularly those with a history of peptic ulcer, diverticulosis or other inflammatory disease of the gastrointestinal tract such as ulcerative colitis and Crohn's disease. In these cases, the physician must weigh the benefits of treatment against the possible hazards.
Physicians should inform patients about the signs and/or symptoms of serious GI toxicity and instruct them to contact a physician immediately if they experience persistent dyspepsia or other symptoms or signs suggestive of GI ulceration or bleeding. Because serious GI tract ulceration and bleeding can occur without warning symptoms, physicians should follow chronically treated patients by checking their haemoglobin periodically and by being vigilant for the signs and symptoms of ulceration and bleeding and should inform the patients of the importance of this follow-up.
If ulceration is suspected or confirmed, or if GI bleeding occurs, ADVIL FLU should be discontinued immediately, appropriate treatment instituted and the patient monitored closely.
No studies, to date, have identified any group of patients not at risk of developing ulceration and bleeding. The major risk factors are a prior history of serious GI events and increasing age. Possible risk factors include other factors such as Helicobacter pylori infection, excess alcohol intake, smoking, female gender and concomitant oral steroid and anticoagulant use. Anti-coagulants, anti-platelet agents (including ASA) or selective serotonin reuptake inhibitors (SSRI’s) have been associated with increased risk. Studies to date show that all NSAIDs can cause GI tract adverse events. Although existing data does not clearly identify differences in risk between various NSAIDs, this may be shown in the future.
There is no definitive evidence that the concomitant administration of histamine H2-receptor antagonists and/or antacids will either prevent the occurrence of gastrointestinal side effects or allow the continuation of ADVIL FLU therapy when and if these adverse reactions appear.
Genitourinary
Some NSAIDs are known to cause persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria or cystitis. The onset of these symptoms may occur at any time after the initiation of therapy with an NSAID. Some cases have become severe on continued treatment. Should urinary symptoms occur, treatment with ADVIL FLU must be stopped immediately to obtain recovery. This should be done before any urological investigations or treatments are carried out.
Diphenhydramine may increase urinary frequency, difficulty in urination, urinary retention and early menses.
Diphenhydramine is not recommended to those with bladder neck obstruction.
Hematologic
Drugs inhibiting prostaglandin biosynthesis do interfere with platelet function to varying degrees; therefore, patients who may be adversely affected by such an action such as those on anti-coagulants or suffering from haemophillia or platelet disorders should be carefully observed when ibuprofen is administered. Numerous studies have shown that the concomitant use of NSAIDs and anti-coagulants increases the risk of bleeding. Concurrent therapy with warfarin requires close monitoring of the international normalized ratio (INR). Even with therapeutic INR monitoring, increased bleeding may occur. (See 9 Drug Interactions – Coumarin-type Anticoagulants)
Blood dyscrasias (such as neutropenia, leukopenia, thrombocytopenia, aplastic anaemia and agranulocytosis) associated with the use of NSAIDs are rare, but could occur with severe consequences.
Diphenhydramine has been implicated with hemolytic anemia, thrombocytopenia, agranulocytosis.
Hepatic/Biliary/Pancreatic
As with other NSAIDs, borderline elevations of one or more liver function tests may occur in up to 15% of patients. These abnormalities may progress, may remain essentially unchanged, or may be transient with continued therapy. A patient with symptoms and/or signs suggesting liver dysfunction, or in whom an abnormal liver test has occurred, should be evaluated for evidence of the development of more severe hepatic reaction while on therapy with this drug. Severe hepatic reactions including jaundice and cases of fatal hepatitis have been reported with NSAIDs.
Although such reactions are rare, if abnormal liver tests persist or worsen, if clinical signs and symptoms consistent with liver disease develop, or if systemic manifestations occur (e.g. eosinophilia, rash, etc.), this drug should be discontinued.
During long-term therapy, liver function tests should be monitored periodically. If there is a need to prescribe this drug in the presence of impaired liver function, it must be done under strict observation.
The frequency of acute liver injury among 625,307 people who received NSAIDs in England and Wales between 1987 and 1991, was examined. There were 311,716 patients who were prescribed ibuprofen. The incidence of acute liver injury among ibuprofen users was 1.6/100,000; this was the lowest incidence among the 8 NSAIDs studied and was significantly lower than the incidence among users of ketoprofen, piroxicam, fenbufen, or sulindac. For NSAID users as a group, the only factors that had an independent effect on the occurrence of acute liver injury were the simultaneous use of hepatotoxic medication or the presence of rheumatoid arthritis. Based on these data, the short-term use of ibuprofen as an analgesic/antipyretic should not be of concern regarding the development of liver disease.
Immune
Ibuprofen: Patients with complete or partial syndrome of nasal polyps, rhinitis or other allergic manifestations should not use ASA or other anti-inflammatory agents. Fatal anaphylactoid reactions have occurred in such individuals even if they have taken NSAIDs in the past without any adverse effects (see 2 Contraindications).
In occasional cases, with some NSAIDs, the symptoms of aseptic meningitis (stiff neck, severe headaches, nausea and vomiting, fever or clouding of consciousness) have been observed. Patients with autoimmune disorders (systemic lupus erythematosus, mixed connective tissue diseases, etc.) seem to be pre-disposed. Therefore, in such patients, the physician must be vigilant to the development of this complication.
Diphenhydramine: Hypersensitivity and anaphylaxis have occurred with diphenhydramine therapy.
Monitoring and Laboratory Tests
General
For Warnings and Precautions related to the use of ADVIL FLU and Monitoring and Laboratory Tests see 7 Warnings and Precautions - Fluid and Electrolyte Balance, 7 Warnings and Precautions - Gastrointestinal, 7 Warnings and Precautions - Hematologic, 7 Warnings and Precautions - Hepatic/Biliary/Pancreatic, 7 Warnings and Precautions - Renal and 7 Warnings and Precautions – 7.1.4 Geriatrics.
Pregnancy
If Advil products are administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women be closely monitored for amniotic fluid volume since these products may result in reduction of amniotic fluid volume and even oligohydramnios (see 7 Warnings and Precautions – 7.1.1 Pregnancy). Advil products are contraindicated for use in the third trimester of pregnancy.
Neurologic
Some patients may experience drowsiness, dizziness, vertigo, insomnia or depression with the use of ibuprofen. If patients experience these side effects, they should exercise caution in carrying out activities that require alertness.
Diphenhydramine delivers a sedative effect. Alcohol and other CNS depressants may increase this effect. Caution should be used when driving a motor vehicle or operating machinery (see 9 Drug Interactions).
Ophthalmologic
Blurred and/or diminished vision has been reported with the use of ibuprofen and other NSAIDs. If such symptoms develop this drug should be discontinued and an ophthalmologic examination performed; ophthalmic examination should be carried out at periodic intervals in any patient receiving this drug for an extended period of time. Patients with glaucoma should not use ADVIL FLU.
Peri-Operative Considerations
In general, NSAIDs are discontinued prior to surgeries to decrease the risk of post-operative bleeding.
Psychiatric
For diphenhydramine, psychosis with hallucinations have been reported. Visual and auditory hallucinations, unintelligible speech and agitation have occurred. (see 7 Warnings and Precautions - Neurologic).
Renal
Long-term administration of NSAIDs to animals has resulted in renal papillary necrosis and other abnormal renal pathology. In humans, there have been reports of acute interstitial nephritis with hematuria, proteinuria, and occasionally nephrotic syndrome.
A second form of renal toxicity has been seen in patients with prerenal conditions leading to the reduction in renal blood flow or blood volume, where prostaglandins have a supportive role in the maintenance of renal perfusion. In these patients, administration of a NSAID may cause a dose dependent reduction in prostaglandin formation and may precipitate overt renal decompensation. Patients at greatest risk of this reaction are those with impaired renal function, heart failure, liver dysfunction, those taking diuretics, and the elderly. Discontinuation of nonsteroidal anti-inflammatory therapy is usually followed by recovery to the pre-treatment state.
Ibuprofen and its metabolites are eliminated primarily by the kidneys; therefore the drug should be used with great caution in patients with impaired renal function. Severely impaired or deteriorating renal function (creatinine clearance <30 mL/min) are at risk. Individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs. In these cases, utilisation of lower doses of ADVIL FLU should be considered and patients carefully monitored.
During long-term therapy kidney function should be monitored periodically.
Respiratory
With diphenhydramine therapy, thickening of bronchial secretions, tightening of chest, wheezing and nasal stuffiness have been reported.
ASA-induced asthma is an uncommon but very important indication of ASA and NSAID sensitivity. It occurs more frequently in patients with asthma who have nasal polyps.
Sensitivity/Resistance
Patients sensitive to any one of the NSAIDs may be sensitive to any of the other NSAIDs also.
Skin
In rare cases, serious skin reactions (e.g., exfoliative dermatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis and erythema multiforme) have been associated with the use of some NSAIDs. Because the rate of these reactions is low, they have usually been noted during post-marketing surveillance in patients taking other medications also associated with the potential development of these serious skin reactions. Thus, causality is NOT clear. These reactions are potentially life threatening but may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that if they experience a skin rash they should discontinue their NSAID and contact their physician for assessment and advice, including which additional therapies to discontinue. NSAIDs should be discontinued at the first appearance of rash or any other sign of hypersensitivity. Diphenhydramine may trigger photosensitivity, excessive perspiration. (see 8 Adverse Reactions - Dermatologic).
7.1 Special Populations
ADVIL FLU is CONTRAINDICATED for use during the third trimester of pregnancy because of risk of premature closure of the ductus arteriosus and the potential to prolong parturition (see 16 Non-Clinical Toxicology).
Caution should be exercised in prescribing Advil products to women who are trying to conceive, during the first and second trimesters of pregnancy, or if breastfeeding (see 16 Non-Clinical Toxicology).
Ibuprofen: Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or embryo-fetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor (such as NSAIDS) in early pregnancy.
In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post-implantation loss and embryo-fetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period.
Diphenhydramine: There are no adequate data from the use of diphenhydramine in pregnant women. The available non-clinical data suggest the potential for diphenhydramine to induce adverse developmental effects when administered to mice (see 16 Non-Clinical Toxicology). The potential risk for humans is unknown. Diphenhydramine crosses the placenta and may cause an increased level of uterine activity and may lead to premature labour. Use of sedating antihistamines during the third trimester may result in reactions in the newborn or premature neonates. Caution should be exercised with its use during the latter part of pregnancy.
Oligohydramnios/Neonatal Renal Impairment
Use of NSAIDs, including Advil products, at approximately 20 weeks gestation or later in pregnancy may cause fetal renal dysfunction leading to oligohydramnios and, in some more severe cases, neonatal respiratory, musculoskeletal and renal problems (see 16 Non-Clinical Toxicology).
Published studies and post-marketing reports describe maternal NSAID use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment, or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. Oligohydramnios is often, but not always, reversible with treatment discontinuation. Complications of prolonged oligohydramnios may, for example, include limb contractures and delayed lung maturation. In some post-marketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If, after careful consideration of alternative treatment options for pain management, NSAID treatment is necessary anywhere from the middle (onset approximately 20 weeks) to the end of the second trimester of pregnancy, it is recommended that the use be limited to the lowest effective dose and shortest duration possible.
Consider ultrasound monitoring of fetal well-being, including of amniotic fluid volume assessment if treatment with Advil products extends beyond 48 hours. It is recommended that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inform pregnant women not to use Advil products and other NSAIDs from the third trimester of pregnancy because of the risk of the premature closing of the fetal ductus arteriosus (see 2 Contraindications). If treatment with Advil products is needed for a pregnant woman anywhere from the middle (onset approximately 20 weeks gestation) to the end of the second trimester of pregnancy, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours.
7.1.2 Breastfeeding
Ibuprofen: The high protein binding and lower pH of breast milk versus plasma tend to inhibit the excretion of ibuprofen into breast milk. One study showed an ibuprofen concentration of 13 ng/mL 30 minutes after ingesting 400 mg. The milk: plasma ratio was 1:126. This translates to an infant exposure of 0.0008% of the maternal dose. It is not known to what extent, if any, ibuprofen crosses the human placenta.
Diphenhydramine: Evidence suggests that diphenhydramine may alter milk production or composition. If an alternative drug is not prescribed, infants’ adequate intake of milk should be monitored. It is not known whether diphenhydramine is excreted into milk. Because of the generally higher risk of antihistamines for infants and for newborns and premature babies, ADVIL FLU is contraindicated in breastfeeding mothers.
7.1.3 Pediatrics
Pediatrics (< 16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ADVIL FLU in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Patients older than 65 years and frail or debilitated patients are most susceptible to a variety of adverse reactions from NSAIDs: the incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. The chance of stomach bleeding is higher if you are: age 60 or older, have had stomach ulcers or bleeding problems, take a blood thinner or steroid drug, take with other drugs containing an NSAID like acetylsalicylic acid (ASA), ibuprofen, naproxen, or prescription anti-inflammatory drugs, have 3 or more alcoholic drinks every day while using this product. Most reports of fatal GI events are in this population. Older patients are also at risk of lower oesophageal ulceration and bleeding.
The elderly are also more susceptible to the side effects of diphenhydramine: dizziness, sedation, disturbed co-ordination, hypotension, confusion and paradoxical excitation.
For such patients, considerations should be given to a starting dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision.
8. Adverse Reactions
8.1 Adverse Reaction Overview
In clinical trials and post-market surveillance, the common (≥1/100 to <1/10) adverse reactions included:
Ibuprofen: diarrhea, dizziness, drowsiness, dyspepsia, headache, nausea and vomiting
Diphenhydramine: disturbance in attention, dizziness, dry mouth, fatigue, sedation, somnolence and unsteadiness.
Adverse reactions are more likely to occur with increasing dose and duration of use.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following convention has been utilised for the classification of the frequency of adverse reactions: very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1,000 to <1/100), rare (≥1/10,000 to <1/1000), very rare (<1/10,000), not known (cannot be estimated from available data).
Studies of Ibuprofen and Diphenhydramine in Combination
In a 10-day maximum use safety and efficacy study (AE-97-08), a total of 1016 patients between 12 to >65 years of age took either one Advil Nighttime liqui-gel (ibuprofen 200 mg/diphenhydramine HCl 25 mg) (n= 158), or two Advil Nighttime liqui-gels (ibuprofen 400 mg/diphenhydramine HCl 50 mg) (n=323), or two Extra Strength Tylenol Nighttime caplets (acetaminophen 1000 mg/diphenhydramine HCl 50 mg) (n=326) or a placebo (N=167) for 10 consecutive evenings. They were instructed to begin taking the study drug on the first evening they experienced sleeplessness associated with a headache or minor aches or pains. They continued to take study medication for the next 9 consecutive evenings, regardless of whether or not they were experiencing symptoms. Although the duration of use was beyond the maximum over-the-counter duration of use (10 days versus 5 days) of ibuprofen, the daily dose was below the maximum daily dose for ibuprofen of 1200 mg and for diphenhydramine of 150 mg. The study suggests that there are no clinically relevant safety concerns associated with Advil Nighttime liqui-gels when administered once a day at a dose of ibuprofen / diphenhydramine hydrochloride (400 mg/50 mg or 200 mg/25 mg).
In this study, although there was an increased incidence of overall nervous system adverse events and somnolence with both doses of Advil Nighttime liqui-gels compared with placebo, these rates were comparable to those observed with two Extra Strength Tylenol Nighttime caplets (acetaminophen 1000 mg/diphenhydramine HCl 50 mg), a marketed analgesic/sleep-aid product consisting of acetaminophen 500 mg/diphenhydramine hydrochloride 25 mg per caplet. The incidences of these symptoms were similar for both doses of ibuprofen / diphenhydramine (400 mg/50 mg vs. 200 mg/25 mg). The AEs with incidence rates exceeding 2% in any treatment group are presented in Table 1. These finding were consistent within all age and gender subgroups.
Table 1: AE-97-08: Adverse Events with Incidence Rates Exceeding 2% in Any Treatment Group
| Number (%) of Subjects with AE Indicated | |||||||||||||||||||||||
| System organ class/preferred term | Placebo (n = 167) | 1 Advil Nighttime Liqui-Gel (n = 158) | 2 Advil Nighttime Liqui-Gels (n = 323) | 2 Extra Strength Tylenol Nighttime Caplets (n = 326) | p-value ** | ||||||||||||||||||
| Gastrointestinal Disorders | 21 (12.6) | 16 (10.1) | 39 (12.1) | 50 (15.3) | 0.411 | ||||||||||||||||||
| Dyspepsia | 15 (9.0) | 11 (7.0) | 16 (5.0) | 25 (7.7) | 0.315 | ||||||||||||||||||
| Dry Mouth | 1 (0.6) | 1 (0.6) | 7 (2.2) | 5 (1.5) | 0.514 | ||||||||||||||||||
| General disorders and administration site conditions | 30 (18.0) | 25 (15.8) | 57 (17.6) | 50 (15.3) | 0.818 | ||||||||||||||||||
| Headache | 17 (10.2) | 12 (7.6) | 37 (11.5) | 28 (8.6) | 0.500 | ||||||||||||||||||
| Pain | 4 (2.4) | 2 (1.3) | 10 (3.1) | 17 (5.2) | 0.134 | ||||||||||||||||||
| Back Pain | 8 (4.8) | 5 (3.2) | 8 (2.5) | 5 (1.5) | 0.185 | ||||||||||||||||||
| Nervous system disorders | 6 (3.6) | 20 (12.7) | 40 (12.4) | 41 (12.6) | 0.004 | ||||||||||||||||||
| Somnolence | 4 (2.4) | 14 (8.9) | 28 (8.7) | 25 (7.7) | 0.032 | ||||||||||||||||||
| Dizziness | 2 (1.2) | 1 (0.6) | 5 (1.5) | 9 (2.8) | 0.414 | ||||||||||||||||||
| Respiratory, thoracic and mediastinal disorders | 7 (4.2) | 9 (5.7) | 9 (2.8) | 10 (3.1) | 0.377 | ||||||||||||||||||
| Rhinitis | 5 (3.0) | 5 (3.2) | 7 (2.2) | 7 (2.1) | 0.815 | ||||||||||||||||||
**: Fisher’s exact test; P-values < 0.05 are bolded.
Two placebo-controlled, double-blind clinical trials (AE-98-01 and AE-98-02) studied subjects 16-45 years of age who had undergone surgical removal of 1 or 2 impacted third molars, one of which was at least a partial bony mandibular impaction, and were given a single dose of either placebo ibuprofen (400 mg) /diphenhydramine (50 mg) or 400 mg ibuprofen (n=118), before bedtime on the day of surgery.
Study AE-98-01 involved 281 subjects, with 40 receiving placebo, 122 receiving ibuprofen (400 mg) /diphenhydramine (50 mg) and 118 receiving 400 mg ibuprofen.
The active treatments were well tolerated. A total of 29 adverse experiences (AEs) were reported by 25 (8.9%) subjects:15.0% in the placebo group, 9.8% in the ibuprofen/diphenhydramine group, and 5.9% in the ibuprofen group. The AEs with incidence rates exceeding 2% in any treatment group are presented in Table 2. The incidence rates were comparable among the three treatment groups with respect to all adverse experiences, except for headache (placebo=10.0%; ibuprofen/diphenhydramine=0.8%; ibuprofen=0.8%). There were no serious AEs.
Table 2. AE-98-01: Adverse Events with Incidence Rates Exceeding 2% in Any Treatment Group
| System organ class/preferred term | Placebo (n = 40) | IBU400/D PH50 (n = 122) | IBU400 (n = 119) | p-value+ |
| Any System organ class Any | 6 (15.0%) | 12 (9.8%) | 7 (5.9%) | 0.175 |
Gastrointestinal disorders Any Nausea Vomiting Abdominal Pain | 1 (2.5%) 0 (0.0%) 0 (0.0%) 1 (2.5%) | 6 (4.9%) 5 (4.1%) 0 (0.0%) 0 (0.0%) | 5 (4.2%) 4 (3.4%) 3 (2.5%) 0 (0.0%) | 1.000 0.587 0.129 0.142 |
General disorders and administration site conditions Any Headache | 4 (10.0%) 4 (10.0%) | 2 (1.6%) 1 (0.8%) | 1 (0.8%) 1 (0.8%) | 0.017* 0.004* |
Nervous system disorders Any Dizziness | 1 (2.5%) 1 (2.5%) | 5 (4.1%) 4 (3.3%) | 0 (0.0%) 0 (0.0%) | 0.069b 0.129 |
+: Fisher’s Exact test; *: Statistically significant at p ≤ 0.05; b: Marginally significant ( 0.05 < p ≤ 0.10).
Study AE-98-02 involved 283 subjects, with 40 receiving placebo, 120 receiving ibuprofen (400 mg) /diphenhydramine (50 mg) and 123 receiving 400 mg ibuprofen. A total of 41AEs were reported by 29 (10.2%) of subjects: 20.0% in the placebo group, 11.7% in the ibuprofen/diphenhydramine group, and 5.7% in the ibuprofen group. The AEs with incidence rates exceeding 2% in any treatment group are presented in Table 3. There was a significant difference among the three treatment groups with respect to overall adverse experiences. There was a significant difference among the groups for digestive system AEs, and for the specific event of vomiting (placebo 5.0%; ibuprofen/diphenhydramine 0.8%; ibuprofen 0.0%). The treatment groups were comparable for other AEs and body systems. There were no serious AEs.
Table 3. AE-98-02: Adverse Events with Incidence Rates Exceeding 2% In Any Treatment Group
| System organ class/preferred term | Placebo (n=40) | IBU400/DPH 50 (n=120) | IBU400 (n=123) | p-value+ |
Any System organ class Any | 8 (20.0%) | 14 (11.7%) | 7 (5.7%) | 0.027* |
Gastrointestinal disorders Any Nausea Vomiting | 6 (15.0%) 5 (12.5%) 2 (5.0%) | 5 (4.2%) 5 (4.2%) 1 (0.8%) | 5 (4.1%) 5 (4.1%) 0 (0.0%) | 0.038* 0.111 0.028* |
General disorders and administration site conditions Any Headache | 2 (5.0%) 2 (5.0%) | 9 (7.5%) 9 (7.5%) | 5 (4.1%) 5 (4.1%) | 0.461 0.461 |
Nervous system disorders Any Agitation | 1 (2.5%) 1 (2.5%) | 2 (1.7%) 0 (0.0%) | 1 (0.8%) 0 (0.0%) | 0.519 0.141 |
Skin and subcutaneous tissue disorders Any Sweating | 1 (2.5%) 1 (2.5%) | 0 (0.0%) 0 (0.0%) | 0 (0.0%) 0 (0.0%) | 0.141 0.141 |
+: Fisher’s Exact test, *: Statistically significant at p ≤ 0.05
Studies of Diphenhydramine
The following reaction has been observed in clinical trials with diphenhydramine hydrochloride:
| System Organ Class | Adverse Reaction | Frequency |
|---|---|---|
| General disorders and administration site conditions | Fatigue | Common |
8.5 Post-Market Adverse Reactions
Safety Studies of Ibuprofen
One researcher conducted an extensive analysis of published data concerning the relative safety of non-prescription doses of ibuprofen and acetaminophen. Of a total of 96 randomized and blinded trials, there were 10 trials of seven days’ duration or less where the safety of both drugs was directly compared. In three of these trials, the incidence of adverse events was higher with acetaminophen; there were no reported adverse events in six trials; and one trial reported a higher incidence with ibuprofen. In this subset of 10 studies, it was reported that gastrointestinal adverse events were found to be the most common type of event reported and were predominantly dyspepsia, nausea, or vomiting. None of the GI events appeared to warrant follow-up from which the author inferred there were no serious gastrointestinal events.
It was concluded: “Although we recognise that the above-mentioned data are very selective and are based on information derived from a variety of trial designs and populations, it is nonetheless instructive for indicating a relatively low incidence of severe adverse reactions with both drugs when taken at their respective non-prescription dosages.”
The results of a double-blind, placebo-controlled study in healthy subjects (N = 1246) representative of a non-prescription analgesic user population indicate that ibuprofen at a dosage of 1200 mg/day for 10 consecutive days is well tolerated. The frequency of GI AEs was similar in the placebo and ibuprofen groups (16% with placebo vs. 19% with ibuprofen). The most frequent GI AEs (those reported by >1% of the subjects) were dyspepsia, abdominal pain, nausea, diarrhoea, flatulence, and constipation. There was no difference between the two groups in the proportion discontinuing treatment because of GI AEs. Seventeen subjects (1.4%) had positive occult blood tests: the frequency was comparable for the two treatments.
In two multi-trial analyses, a meta-analysis, and a literature review, ibuprofen had a low incidence of GI drug reactions, comparable with that of acetaminophen and placebo.
A large-scale randomized trial comparing non-prescription doses of acetylsalicylic acid, acetaminophen, and ibuprofen in 8677 adults found that the rates of significant adverse reactions were: ASA 18.7%, ibuprofen 13.7%, and acetaminophen 14.5%. Ibuprofen was not statistically different from acetaminophen. Total GI events (including dyspepsia) and abdominal pain were less frequent with ibuprofen (4% and 2.8%, respectively) than with acetaminophen (5.3% and 3.9%) or ASA (7.1% and 6.8%) [all p < 0.035]. It was concluded that “The overall tolerability of ibuprofen in this large-scale study was equivalent to that of paracetamol and better than that of [ASA].”
In epidemiological studies, ibuprofen has consistently exhibited the lowest relative risk of severe gastrointestinal complications compared with other NSAIDs and ASA. No symptom or syndrome emerged in the trials that was not predicted from the drug’s pharmacology or could not have been anticipated based on ibuprofen’s extensive use as an analgesic/antipyretic in adults.
Another study reported on the frequency of acute liver injury among 625,307 people who received NSAIDs in England and Wales between 1987 and 1991, of whom 311,716 were prescribed ibuprofen. The incidence of acute liver injury among ibuprofen users was 1.6/100,000. This was the lowest incidence among the eight NSAIDs studied and was significantly lower than the incidence among users of ketoprofen, piroxicam, fenbufen, or sulindac. For NSAID users as a group, the only factors that had an independent effect on the occurrence of acute liver injury were simultaneous use of hepatotoxic medication and the presence of rheumatoid arthritis (see 7 Warnings and Precautions - Hepatic/Biliary/Pancreatic).
Adverse Events with Doses of Ibuprofen ≥1200 mg/day
The following adverse events have been noted in patients treated with prescription doses
(≥1200 mg/day).
Gastrointestinal
In clinical trials of NSAIDs, symptomatic upper GI ulcers, gross bleeding, or perforation occurred in approximately 1% of patients treated for 3-6 months and in about 2-4% of patients treated for 1 year. The risk continues beyond 1 year. The incidence of GI complications increases with increasing dose.
Incidence 3-9%: nausea, epigastric pain, heartburn. Incidence 1-3%: diarrhoea, abdominal distress, nausea and vomiting, indigestion, constipation, abdominal cramps or pain, fullness of the GI tract (bloating or flatulence).
Incidence <1%: gastric or duodenal ulcer with bleeding and/or perforation, gastrointestinal haemorrhage, melena, hepatitis, jaundice, abnormal liver function (SGOT, serum bilirubin and alkaline phosphatase).
Allergic
Incidence <1%: anaphylaxis (See 2 Contraindications). Causal relationship unknown: fever, serum sickness, lupus erythematosus.
Central Nervous System
Incidence 3-9%: dizziness. Incidence 1-3%: headache, nervousness. Incidence <1%: depression, insomnia. Causal relationship unknown: paraesthesias, hallucinations, abnormal dreams.
Aseptic meningitis and meningoencephalitis, in one case accompanied by eosinophilia in the cerebrospinal fluid, have been reported in patients who took ibuprofen intermittently and did not have any connective tissue disease.
Dermatologic
Incidence 3-9%: rash (including maculopapular type). Incidence 1-3%: pruritus. Incidence <1%: vesiculobullous eruptions, urticaria, erythema multiforma. Causal relationship unknown: alopecia, Stevens-Johnson syndrome.
Cardiovascular
Incidence <1%: congestive heart failure in patients with marginal cardiac function, elevated blood pressure, palpitations. Causal relationship unknown: arrhythmias (sinus tachycardia, sinus bradycardia, palpitations).
Special Senses
Incidence 1-3%: tinnitus. Incidence <1%: amblyopia (blurred and/or diminished vision, scotomata, and/or changes in colour vision). Causal relationship unknown: conjunctivitis, diplopia, optic neuritis.
Haematologic
Incidence <1%: leukopenia, decreases in haemoglobin and haematocrit. Causal relationship unknown: haemolytic anaemia, thrombocytopenia, granulocytopenia, bleeding episodes (e.g., purpura, epistaxis, haematuria, menorrhagia).
Hepatic
Liver enzyme elevations may occur in up to 15% of patients treated with ibuprofen. .
Renal
Acute interstitial nephritis with hematuria, proteinuria, and occasionally nephrotic syndrome have been reported. Renal papillary necrosis has been reported. Causal relationship unknown: decreased creatinine clearance, polyuria, azotemia.
Endocrine
Causal relationship unknown: gynecomastia, hypoglycaemic reaction. Menstrual delays of up to 2 weeks and dysfunctional uterine bleeding occurred in nine patients taking ibuprofen, 400 mg t.i.d., for three days before menses.
Metabolic
Incidence 1-3%: decreased appetite, oedema, fluid retention.
Additional Adverse Reactions Observed During Post-Market Surveillance
Ibuprofen
| System Organ Class | Adverse Reaction | Frequency |
|---|---|---|
| Blood and lymphatic system disorders | Pancytopenia | Very rare |
| Cardiac disorders | Myocardial infarction | Very rare |
| Gastrointestinal disorders | Intestinal diaphragm disease | Rare |
Perforation or gastrointestinal haemorrhage, sometimes fatal, particularly in the elderly. Exacerbation of ulcerative colitis and Crohn’s disease. | Very rare | |
| Hepatobiliary disorders | Liver disorders, hepatic failure, hepatitis. | Very rare |
| Immune system disorders | Exacerbation of asthma and bronchospasm. | Very rare |
| Renal and urinary disorders | Acute renal failure. | Very rare |
| Skin and subcutaneous tissue disorders | Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), Toxic Epidermal Necrolysis (TEN) | Very rare |
Diphenhydramine
As these reactions are reported voluntarily from a population of uncertain size, the frequency of these reactions is not known but likely to be rare or very rare (<1/1000)
| System Organ Class | Adverse Reaction | Frequency |
|---|---|---|
| Musculoskeletal and connective tissue disorders | Muscle twitching | Not known |
| Nervous system disorders | Convulsions, dyskinesias. | Not known |
| Psychiatric disorders | Confusion | Not known |
9. Drug Interactions
9.1 Serious Drug Interactions
- acetylsalicylic acid (ASA), other NSAIDs including ibuprofen and other analgesics may result in possible additive side effects (see 9.4 Drug-Drug Interactions - Acetylsalicylic acid (ASA) or other NSAIDs).
- anticoagulants may increase the risk of GI adverse events (e.g., ulceration and bleeding) (see 9.4 Drug-Drug Interactions – Coumarin-Type Anticoagulants).
- cyclosporin may increase the risk of nephrotoxicity (see 9.4 Drug-Drug Interactions – Cyclosporin).
- digoxin may increase serum digoxin concentration and the risk of digoxin toxicity (see 9.4 Drug-Drug Interactions - Digoxin).
- diphenhydramine may potentiate the sedative effects of alcohol, other CNS depressants such as tranquilisers, sleep-aids and other antihistamines. (see 9.4 Drug-Drug Interactions – CNS Depressant Drugs)
- glucocorticoids may increase the risk of GI adverse reactions, including ulceration and bleeding (see 9.4 Drug-Drug Interactions – Glucocorticoids).
- hypoglycaemic agents (oral agents and insulin) may increase the risk of hypoglycaemia (see 9.4 Drug-Drug Interactions – Hypoglycaemic Agents).
- lithium may elevate plasma lithium levels, reduce renal lithium clearance and increase the risk of lithium toxicity (see 9.4 Drug-Drug Interactions – Lithium).
- methotrexate may increase the risk of methotrexate toxicity (see 9.4 Drug-Drug Interactions – Methotrexate).
- monoamine oxidase inhibitors (MAOI’s) may prolong and intensify the anticholinergic effects of diphenhydramine (see 9.4 Drug-Drug Interactions – MAOI’s)
- selective serotonin reuptake inhibitors (SSRIs) may increase the risk of GI bleeding (see 9.4 Drug-Drug Interactions - Selective serotonin reuptake inhibitors).
- quinolone antibiotics may increase the risk of convulsions (see 9.4 Drug-Drug Interactions – Quinolones).
9.2 Drug Interactions Overview
ADVIL FLU is not recommended for concomitant use with any other NSAIDs, including ASA. Documented or possible drug interactions with ADVIL FLU include acetaminophen, naproxen, alcohol and other CNS depressant drugs, antihypertensives, anticoagulants, digoxin, diuretics, lithium, methotrexate, oral antidiabetic agents and insulin, and other protein-bound drugs.
9.3 Drug-Behaviour Interactions
Because of the possibility of additive CNS depressant effects, patients should avoid alcoholic beverages when taking ADVIL FLU. (see 7 Warnings and Precautions - Neurologic).
9.4 Drug-Drug Interactions
The drugs listed in this section are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Acetaminophen
Although interactions have not been reported, concurrent use with ADVIL FLU is not advisable: it may increase the risk of adverse renal effect.
Acetylsalicylic acid (ASA) or other NSAIDs
The use of ADVIL FLU in addition to any other NSAID, including ASA, is not recommended because of the absence of any evidence demonstrating synergistic benefits and the potential for additive side effects. Animal studies show that ASA given with NSAIDs, including ibuprofen, yields a net decrease in anti-inflammatory activity with lowered blood levels of the non-ASA drug. Single-dose bioavailability studies in normal volunteers have failed to show an effect of ASA on ibuprofen blood levels. Correlative clinical studies have not been conducted (see 2 Contraindications).
No clinically meaningful loss of cardio-protection was observed, when patients on low dose ASA (81 mg) were administered 400 mg ibuprofen T.I.D., keeping in mind that combination NSAID therapy is associated with additive adverse reactions.
Acetylsalicylic acid (ASA) Low Dose
Ibuprofen can interfere with the anti-platelet effect of low-dose ASA (81 - 325 mg per day). Long-term daily use of ibuprofen may render ASA less effective when used for cardio-protection and stroke prevention. To minimize this interaction, regular users of ibuprofen and low-dose, immediate-release ASA should take the ibuprofen at least one hour after or 11 hours before the daily low-dose ASA. The use of delayed-release (e.g. enteric coated) ASA is not recommended when using ibuprofen regularly. Healthcare professionals should advise consumers and patients regarding the appropriate concomitant use of ibuprofen and ASA.
Aminoglycosides
Reduction in renal function in susceptible individuals, decreased elimination of aminoglycoside and increased plasma concentrations.
Antacids
A bioavailability study has shown that there was no interference with the absorption of ibuprofen when given in conjunction with an antacid containing aluminium hydroxide and magnesium hydroxide.
Antihypertensives
Prostaglandins are an important factor in cardiovascular homeostasis and inhibition of their synthesis by NSAIDs may interfere with circulatory control. NSAIDs may elevate blood pressure in patients receiving antihypertensive medication. Two meta-analyses have observed this relationship for NSAIDs as a class and for certain NSAIDs in particular, but ibuprofen did not significantly affect blood pressure in either meta-analysis. Consistent with this lack of effect, a study by Davies et al showed that ibuprofen 1600 mg/day for 14 days did not attenuate the antihypertensive effect of two β-adrenergic blockers. Houston et al showed no effect of three weeks’ therapy with ibuprofen on the antihypertensive efficacy of verapamil, but it is not known whether this lack of interaction extends to other classes of calcium channel blockers.
When renal perfusion pressure is reduced both prostaglandins and angiotensin II are important mediators of renal autoregulation. As a class, the combination of an NSAID and angiotensin converting enzyme inhibitor theoretically may have the potential to decrease renal function. One study found a clinically significant decrease in renal function in 4 of 17 patients treated with hydrochlorothiazide and fosinopril who received ibuprofen 2400 mg/day for one month. In contrast, Minuz found no effect on the antihypertensive effect of enalapril or on plasma renin or aldosterone following two days’ treatment with ibuprofen 1200 mg/day.
The relationship of ibuprofen and antihypertensives is clearly not well defined. The benefits of concomitant medication should be analysed and compared to the potential risks before being prescribed. If ibuprofen is being recommended for long-term use, then periodic monitoring of blood pressure may be useful. Blood pressure monitoring is not necessary if ibuprofen is being recommended for short-term use as an analgesic.
Apomorphine
Diphenhydramine may decrease the emetic response of apomorphine in the treatment of poisoning.
CNS Depressant Drugs
Antidepressants such as amitriptyline, amoxapine, belladonna alkaloids, clomipramine, procarbazine and triflupromazine may increase the possibility of dry mouth, urinary retention, adynamic ileus, chronic glaucoma and altered mental status.
Caution is necessary if ADVIL FLU is taken with other antihistamines, tranquilizers or any other sedating drug (encompassing any other diphenhydramine product including topical applications) or with prescription drugs used to treat depression.
Coumarin-type Anticoagulants
Numerous studies have shown that the concomitant use of NSAIDs and anticoagulants increases the risk of GI adverse events such as ulceration and bleeding. Because prostaglandins play an important role in hemostasis, and NSAIDs affect platelet function, concurrent therapy of ibuprofen with warfarin requires close monitoring to be certain that no change in anticoagulant dosage is necessary. Several short-term controlled studies failed to show that ibuprofen significantly affected prothrombin time or a variety of other clotting factors when administered to individuals on coumarin-type anticoagulants. Nevertheless, the physician should be cautious when administering Advil products to patients on anticoagulants.
Cyclosporin
There is an increased risk of nephrotoxicity.
CYP2C9 inhibitors
Concomitant administration of ibuprofen with CYP2C9 inhibitors may increase the exposure to ibuprofen (CYP2C9 substrate). In a study with voriconazole and fluconazole (CYP2C9 inhibitors), an increased S(+)-ibuprofen total exposure (AUC) by approximately 80 to 100% has been shown. Reduction of the ibuprofen dose should be considered when potent CYP2C9 inhibitors are administered concomitantly, particularly when high-dose ibuprofen is administered with either voriconazole or fluconazole.
Digoxin
Ibuprofen has been shown to increase serum digoxin concentration. NSAIDS may exacerbate cardiac failure and reduce GFR. Increased monitoring and dosage adjustments of digitalis glycoside may be necessary during and following concurrent ibuprofen therapy.
Diuretics
Clinical studies, as well as random observations, have shown that ibuprofen can reduce the natriuretic effect of furosemide and thiazides in some patients. This response has been attributed to inhibition of renal prostaglandin synthesis. During concomitant therapy with ibuprofen, the patient should be observed closely for signs of renal failure as well as to assure diuretic efficacy.
Drugs primarily metabolised by CYP2D6
Diphenhydramine is an inhibitor of the cytochrome (CYP) p450 isoenzyme CYP2D6. Therefore, there may be a potential for interaction with drugs which are primarily metabolised by CYP2D6, such as metoprolol and venlafaxine.
Glucocorticoids
Some studies have shown that the concomitant use of NSAIDs and oral glucocorticoids increases the risk of GI adverse events such as ulceration and bleeding. This is especially the case in older (> 65 years of age) individuals. Caution should be used when taking ibuprofen products in conjunction with corticosteroids.
H-2 antagonists
In studies with human volunteers, coadministration of cimetidine or ranitidine with ibuprofen had no substantive effect on ibuprofen serum concentrations.
Hypoglycaemic Agents
Ibuprofen may increase hypoglycaemic effects of oral antidiabetic agents and insulin.
Lithium
Ibuprofen produced an elevation of plasma lithium levels and a reduction in renal lithium clearance in a study of eleven normal volunteers. The mean minimum lithium concentration increased 15% and the renal clearance of lithium was decreased by 19% during this period of concomitant drug administration. This effect has been attributed to inhibition of renal prostaglandin synthesis by ibuprofen. Thus, when ibuprofen and lithium are administered concurrently, subjects should be observed carefully for signs of lithium toxicity.
Methotrexate
Ibuprofen as well as other NSAIDs has been reported to competitively inhibit methotrexate accumulation in rabbit kidney slices. This may indicate that ibuprofen could enhance the toxicity of methotrexate. Caution should be used when ibuprofen is administered concomitantly with methotrexate. Renal function should be monitored.
Monoamine Oxidase Inhibitors (MAOIs)
MAOIs, including furazolidone and procarbazine, may prolong and intensify the anticholergic and CNS depressant effects of diphenhydramine.
Use with caution in patients taking MAOIs or within 2 weeks of stopping an MAOI.
Diphenhydramine should not be given to patients taking Eldepryl, Marplan, Nardil or Parnate.
Naproxen
Although interactions have not been reported, concurrent use with ADVIL FLU is not advisable: it may increase the risk.
Quinolones
NSAIDs can increase the risk of convulsion associated with quinolone antibiotics.
Selective Serotonin Reuptake Inhibitors (SSRIs)
Studies report an increased risk of gastrointestinal (GI) ulceration and bleeding when Ibuprofen as well as other NSAIDs are taken concomitantly with selective serotonin reuptake inhibitors (SSRIs) than when either class of drugs is taken alone (see 7 Warnings and Precautions - Gastrointestinal).
Zidovudine
There is an increased risk of haemarthroses and haematoma in HIV (+) haemophiliacs.
Other Drugs
Although ibuprofen binds extensively to plasma proteins, interactions with other protein-bound drugs occur rarely. Nevertheless, caution should be observed when other drugs, also having a high affinity for protein binding sites, are used concurrently. No interactions have been reported when ibuprofen has been used in conjunction with probenecid, thyroxine, steroids or benzodiazepines. Caution should be used when taking ibuprofen products in conjunction with antibiotics.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbs have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1 Mechanism of Action
Ibuprofen
Like other nonsteroidal anti-inflammatory drugs (NSAIDs), ibuprofen is an analgesic, antipyretic, and anti-inflammatory medication. The principal mechanism of action of ibuprofen and other NSAIDs is inhibition of prostaglandin biosynthesis.
Prostaglandins are naturally occurring fatty acid derivatives that are widely distributed in the tissues. They are believed to be a common factor in the production of pain, fever, and inflammation. Prostaglandins are believed to sensitize tissues to pain- and inflammation-producing mediators such as histamine, 5-hydroxytryptamine, and kinins. The enzyme catalysing the committed step in prostaglandin biosynthesis is prostaglandin endoperoxide synthase, also known as cyclooxygenase. There is significant evidence that the main mechanism of analgesic/antipyretic action of NSAIDs is prostaglandin biosynthesis inhibition. Other pharmacologic effects such as lysosome and plasma membrane stabilisation have been observed, but the potential relevance of these effects to ibuprofen-induced analgesia and antipyresis is unclear.
Diphenhydramine Hydrochloride
Diphenhydramine is a first generation H1 receptor inverse agonist of the ethanolamine class that is available over-the counter for use as a sedative, hypnotic, antihistamine, antitussive, and antiemetic agent.
Most antihistamines cross the blood-brain barrier and produce sedation due to inhibition of histamine N-methyltransferase and blockage of central histaminergic receptors. Antagonism of other central nervous system receptor sites, such as those for serotonin, acetylcholine, and alpha-adrenergic stimulation, may also be involved.
10.2 Pharmacodynamics
Ibuprofen
Animal Pharmacology
Cyclooxygenase inhibitors such as ibuprofen and other NSAIDs reduce thromboxane A2 production and release, thereby decreasing platelet aggregation. Like many other NSAIDs, ibuprofen inhibits platelet aggregation, as demonstrated in vivo by prevention of platelet disposition in aortopulmonary arterial bypass grafts in dogs. The drug’s protective action against pulmonary embolism in rabbits injected intravenously with arachidonic acid may also relate to inhibition of platelet aggregation. The decreased platelet aggregation may be due in part to a reduction in membrane fluidity. Ibuprofen may also reduce platelet membrane fluidity, which reduces aggregation, but it is not known to what extent TXA2 synthesis inhibition is involved in this effect.
The penetration of ibuprofen into rabbit and rat foetuses was investigated. Rabbits and rats in late pregnancy were given single oral doses of 60 and 20 mg/kg respectively of C14-labeled ibuprofen. Rabbits were killed 3 hours after dosing, and rats were killed 1.5 hours after dosing. Blood samples were collected from the mothers and foetuses. The concentrations of radioactively labelled material were similar in maternal and foetal blood, indicating that ibuprofen and its metabolites readily crossed the placenta and entered the foetal circulation.
Human Pharmacology
Two metabolites of ibuprofen were isolated from the urine of patients who had been treated for one month with the drug. The metabolites were identified as 2-[4-(2-hydroxy-2-methylpropyl] phenyl propionic acid (metabolite A) and 2-[4-(2-carboxypropyl)phenyl] propionic acid (metabolite B). About 1/3 of the dose was excreted in the urine of patients as metabolite B, 1/10 as unchanged ibuprofen and 1/10 as metabolite A. The remainder of the dose could not be identified in the urine.
In healthy volunteers, platelet aggregation decreased significantly at a dosage of 1800 mg per day of ibuprofen given over a period of 28 days. Ibuprofen influenced ADP-induced aggregation to a lesser extent than collagen-induced aggregation. Platelet aggregation induced by recalcification of citrated platelet-rich plasma (a thrombin-induced reaction) was not influenced by ibuprofen treatment. Likewise, ibuprofen did not affect whole blood clotting time on recalcification or prothrombin time. Bleeding time measured 2 hours after administration of ibuprofen showed a significant, dose-related increase.
Diphenhydramine Hydrochloride
Human Pharmacology
Seven intensive care patients were studied for the effects of cimetidine, an H2 antagonist on cardiovascular parameters with and without premedication. Cimetidine 200 mg was administered IV on Day 1. Mean arterial pressure dropped within 2 minutes and remained below baseline for the 8 minute measurement period. Diphenhydramine, an H1inverse agonist, was administered as 40 mg IV 5 minutes before administering cimetidine 200 mg IV on day 2. Mean arterial pressure did not change. The authors concluded that cimetidine has enough H1-receptor characteristics to affect blood pressure.
10.3 Pharmacokinetics
Absorption
Ibuprofen
Ibuprofen is a racemic mixture of R-(-) ibuprofen and S-(+) ibuprofen. R-(-) ibuprofen undergoes extensive (53% to 65%) enantiomeric conversion to S-(+) ibuprofen in humans, averaging between 53-65%. S-(+) ibuprofen is the pharmacologically active enantiomer.
Ibuprofen is rapidly absorbed after oral administration. Serum concentrations reach a peak within 1 to 2 hours in adults and in children. Food decreases the rate but not the extent of ibuprofen absorption.
Diphenhydramine Hydrochloride
Diphenhydramine hydrochloride is well-absorbed following oral administration, but undergoes first-pass metabolism in the liver and only about 40-60% of an oral dose reaches systemic circulation as unchanged diphenhydramine.
Following oral administration of a single dose of diphenhydramine, the drug appears in plasma within 15 minutes and peak plasma concentrations are attained within 1-4 hours.
Following oral administration of diphenhydramine hydrochloride dosages of 25 mg every 4 hours or 50 mg every 6 hours, peak steady-state plasma concentrations of the drug were 55 or 85 ng/mL, respectively, and minimum peak steady-state plasma concentrations were 27.5 or 30 ng/mL, respectively.
Distribution
Ibuprofen
After oral administration, the volume of distribution of ibuprofen was 0.1–0.2 L/kg in adults. At therapeutic concentrations, ibuprofen is extensively bound to whole human plasma and binds primarily to site II of purified albumin.
Diphenhydramine Hydrochloride
The distribution of diphenhydramine into human body tissues and fluid has not been fully characterized. Following IV administration in rats, highest concentrations of the drug are attained in the lungs, spleen, and brain, with lower concentrations in the heart, muscle, and liver. Following IV administration in healthy adults, diphenhydramine reportedly has an apparent volume of distribution of 188-366L. The volume of distribution of the drug reportedly is larger in Asian (about 480 L) than in Caucasian adults. The drug crosses the placenta and has been detected in milk, although the extent of distribution in milk has not been quantified.
Diphenhydramine is approximately 80-85% bound to plasma proteins in vitro. Less extensive protein binding of the drug has been reported in healthy Asian adults and in adults with liver cirrhosis.
Metabolism
Ibuprofen
The plasma half-life (t½) of ibuprofen in adults and children is 1.5-2.0 hours. There is no appreciable plasma accumulation of ibuprofen or its metabolites with repeated doses. Two major metabolites, 2-[4-(2-carboxypropyl)phenyl] propionic acid and 2-[4-(2-hydroxy-2-methylpropyl] phenyl propionic acid, have been identified in plasma and in urine. The metabolites 1-hydroxyibuprofen and 3-hydroxyibuprofen have also been found in urine in very small concentrations. Bile and faeces are relatively minor elimination routes. Approximately 80% of an ibuprofen dose is recovered in urine within 24 hours, primarily as carboxymetabolites and hydroxymetabolites, both conjugated and unconjugated.
Cytochrome P450 (CYP) 2C9 has been identified as the most important enzyme in the oxidative metabolism of R-(-) and S-(+) ibuprofen. Ibuprofen does not appear to induce the formation of drug-metabolizing enzymes in rats.
There is no evidence of changes in metabolism or elimination of ibuprofen with advanced age. A pharmacokinetic evaluation of ibuprofen in subjects 65 to 78 years of age compared with young adult subjects (22 to 35 years of age) found no clinically significant difference in the pharmacokinetic profiles of ibuprofen for the two age groups. Furthermore, there was no statistically significant difference between the two age groups in the urinary excretion pattern of the drug and its major metabolites.
Diphenhydramine Hydrochloride
Diphenhydramine is rapidly and apparently almost completely metabolized. Following oral administration, the drug undergoes substantial first-pass metabolism in the liver. Diphenhydramine appears to be metabolized principally to diphenylmethoxyacetic acid, which may further undergo conjugation. The drug also undergoes dealkylation to form N-demethyl and N, N-didemethyl derivatives. Diphenhydramine and its metabolites are excreted principally in the urine.
Elimination
Ibuprofen
Ibuprofen is rapidly excreted in breast milk. Thirty minutes after oral ingestion of 400 mg of ibuprofen, the concentration in breast milk was found to be 13 ng/mL. The milk:plasma ratio was 1:126, and the exposure of a suckling infant to ibuprofen was calculated to be approximately 0.0008% of the maternal dose. Studies in animals indicate that ibuprofen is transported across the placenta.
Diphenhydramine Hydrochloride
Plasma concentrations of diphenhydramine appear to decline in a monophasic manner, although some pharmacokinetic data suggest a polyphasic elimination. The terminal half-life of diphenhydramine has not been fully elucidated, but appears to range from 2.4-9.3 hours in healthy adults. The terminal elimination half-life reportedly is prolonged in adults with liver cirrhosis.
Following oral administration of a single 100 mg dose of diphenhydramine in healthy adults, about 50-75% of the dose is excreted in the urine in 4 days, almost completely as metabolites and with most urinary excretion occurring within the first 4-48 hours. Only about 1% of a single oral dose is excreted unchanged in the urine.
The total body clearance of diphenhydramine decreases with age. For example, after a single 1.25 mg/kg oral (syrup) dose, the total body clearance for the elderly and children were 11.7 ± 3.1 mL/min/kg versus 49.2 ± 22.8 mL/min/kg, respectively.
The elimination half-life of diphenhydramine is prolonged with age. After a single dose administration of diphenhydramine syrup 1.25 mg/kg, elderly patients exhibited a mean half-life of 13.5 hours compared with 9.2 hours in young adults and 5.4 hours in children.
Special Populations and Conditions
Clinical pharmacology in special populations has not been evaluated.
11. Storage, Stability and Disposal
ADVIL FLU should be stored in tightly closed containers at room temperature (15-30°C).
Others:
Keep in a safe place out of the reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Ibuprofen
Chemical name: α-methyl-4-(2-methylpropyl) benzeneacetic acid
Other names: p-isobutylhydratropic acid 2-(4-isobutylphenyl)-propionic acid
Molecular formula and molecular mass: C13H1802
206.28 daltons
Structural formula:
Physical properties: White or almost white powder or crystals with a characteristic odour.
Solubility: Low solubility in water (<0.1 mg/mL), soluble 1 in 1.5 of alcohol, 1 in 1 of chloroform, 1 in 2 of ether, and 1 in 1.5 of acetone. Ibuprofen is also soluble in an aqueous solution of alkali hydroxides and carbonates.
pKa value: pKa = 4.43
Melting Point: 75 - 78°C
Pharmaceutical standard (if applicable): USP
CH3 COOH CH3 H3C |
|---|
Diphenhydramine Hydrochloride
Non-proprietary name of the drug substance(s): Diphenhydramine hydrochloride
Chemical name: O-benzhydryldimethylaminoethanol hydrochloride (or N-dimethylethylamine hydrochloride or 2-(diphenylmethoxy)-N,N-dimethylethanamine hydrochloride)
Molecular Formula and molecular mass: C17H21NO.HCl
Structural Formula:
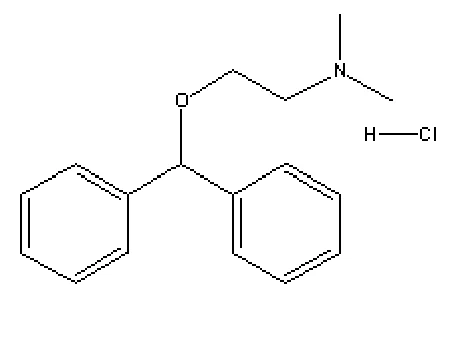
=Physicochemical properties: White, odourless, crystalline powder which slowly darkens on exposure to light. Diphenhydramine has a solubility of 1 g/mL in water and 0.5 g/mL in alcohol at 25°C, pKa = 9, and the onset of melting occurs at about 166-170°C
Pharmaceutical standard: USP
14. Clinical Trials
14.1 Clinical Trials by Indication
Studies with Ibuprofen
Published studies have documented the efficacy of 200 mg and 400 mg doses of ibuprofen in treating mild to moderate pain, including sore throat pain, headache, dental pain, muscle aches, and dysmenorrhea in adults. The antipyretic efficacy of ibuprofen has been demonstrated at doses of 200 and 400 mg in adults.
Studies with Diphenhydramine Hydrochloride
The antihistaminic activity of diphenhydramine has been assessed by measuring the suppression of wheal and flare reaction following histamine skin testing. Plasma diphenhydramine levels above 20 ng/mL have been found to be associated with suppression of wheal and flare formation following a single 50 mg oral dose; antagonism of wheal formation stopped when plasma diphenhydramine levels fell below 20 ng/mL. Diphenhydramine 50 mg was administered to subjects either orally or intravenously. There was a positive correlation between plasma diphenhydramine level and sedative and antihistamine effects, but wide variation in the extent and rate of change of these effects were observed between the subjects. Regardless of route of administration, there appears to be a plasma concentration range of 25 to 50 ng/ml, within which there is significant antihistamine effect without significant sedation. A single oral dose of diphenhydramine 1.25 mg/kg administrated to elderly adults, young adults, and children (mean dose 86, 88 and 40 mg, respectively) produced more pronounced antihistaminic response in children than in the young and elderly adults. The values for Emax were 35.3, 45.7 and 99.8% in the elderly, young adults and children, respectively, while EC50 values were 7.8, 8.0 and 38.7 ng/mL, respectively. The Emax value is the maximum effect attributable to the drug and the EC50 value is the drug concentration producing 50% of the Emax.
Diphenhydramine Hydrochloride has been established as an effective antitussive due to a central mechanism involving the medullary cough centre. A peripheral action may also contribute to its effectiveness although further studies are necessary to define this.
15. Microbiology
No microbiological information is required for this product.
16. Non-Clinical Toxicology
General Toxicology:
Ibuprofen
Single-dose toxicity studies have been conducted in mice, rats, and dogs. The LD50 values for ibuprofen in mice and rats, expressed as mg/kg of body weight, are as follows:
| SPECIES | ROUTE | APPROXIMATE LD50 (mg/kg) |
|---|---|---|
| Mouse | Oral | 800 |
| Rat | Oral | 320 |
| Mouse | Intraperitoneal | 1600 |
| Rat | Subcutaneous | 1300 |
Acute signs of poisoning were prostration in mice and sedation, prostration, loss of righting reflex, and laboured respiration in rats. Death occurred within 3 days from perforated gastric ulcers in mice and intestinal ulceration in rats, irrespective of the route of administration. Single ibuprofen doses of 125 mg/kg and above in dogs caused emesis, transient albuminuria, faecal blood loss, and erosions in the gastric antrum and pylorus. No ill effects were seen with doses of 20 or 50 mg/kg.
The primary toxic effect of ibuprofen in repeated doses in rats is intestinal damage. At a dosage of 180 mg/kg/day for 26 weeks, ibuprofen alters the organ-to-body weight ratio of certain organs, such as the liver, kidneys, gonads, and secondary sex organs, although no histological abnormalities have been observed and the effects are reversible. The liver and kidney enlargement may be a reflection of work hypertrophy associated with the metabolism and excretion of the compound, whereas the significance of the effects on other organs is unknown. When administered in lethal doses (540 mg/kg/day), ibuprofen produces mild kidney lesions in addition to intestinal damage.
In rats given 180 mg/kg/day of ibuprofen orally for 55 weeks and 60 mg/kg/day for the next 60 weeks, the only specific pathological effect observed was intestinal ulceration. There was no evidence of tumour induction, indicating that ibuprofen is not carcinogenic in rats. Ibuprofen is not teratogenic when given in toxic doses (60 mg/kg/day) to rabbits or in ulcerogenic doses (180 mg/kg/day) to rats.
Diphenhydramine Hydrochloride
The LD50 value for diphenhydramine hydrochloride in rats is 500 mg/kg.
Reproduction studies in rats and rabbits receiving diphenhydramine hydrochloride dosages up to five times the recommended human dosage have not revealed evidence of harm to the fetus or impaired fertility.
Oral administration of diphenhydramine to mice during the period of organogenesis at doses ranging from 0.7- to 3.56-fold the recommended maximum clinical dose (based on human equivalent dose) resulted in decreases in maternal weight gain in dams of the higher dose groups. Additionally, there was a decrease in average foetal body weight per litter and a dose related increase in the incidence of cleft palate in higher dose groups.
Ibuprofen and Diphenhydramine Hydrochloride
Acute Toxicity Studies
The LD50 values for ibuprofen, diphenhydramine and ibuprofen/diphenhydramine combination in rats, expressed as mg/kg of body weight, are as follows:
| LD50 (mg/kg) | ||
|---|---|---|
| Ibuprofen | 1225 | |
| Diphenhydramine | 275 | |
| IBU/DPH Combination | 2:1 | 700 |
| 4:1 | 840 | |
| 8:1 | 880 |
No toxicological interactions between the two drugs were observed.
Repeat Dose Toxicity Studies
In the 2- and 13-week repeat-dose toxicity studies rats given ibuprofen alone or in combination with diphenhydramine showed no definite difference in the findings in the drug combinations given at 4:1 or 8:1. In the 2-week study, the no observable effect level (NOEL) for the drug combination of ibuprofen and diphenhydramine was determined to be 24 mg/kg/day and 6 mg/kg/day, respectively.
In the 13-week study, rats given ibuprofen alone (16 mg/kg/day) or in combination with diphenhydramine (50:12.5 and 100:25 mg/kg/day) showed renal papillary necrosis or edema, or both. In addition, rats in these groups showed gastrointestinal (GI) toxicity characteristic of propionic acid non-steroidal anti-inflammatory drugs (NSAIDs). Secondary effects included decreased hemograms suggesting GI bleeding, which is a characteristic adverse effect from treatment with NSAIDs. There was no indication that the ibuprofen effect was potentiated by the addition of diphenhydramine. A NOEL was calculated for the drug combination of 25:6.25 mg/kg/day.
In dogs, the data from all parameters and examinations did not suggest that any adverse effect of the drug combination was different than those seen from the individual components. However, dogs were given considerably lower doses of ibuprofen and diphenhydramine, alone and in combination, compared to those used to dose rats. It is well known that dogs are more sensitive to the adverse effects of NSAIDs, especially ibuprofen, compared to rats; therefore, it was appropriate to use the lower doses in dogs. In the 2-week study, no result from any examination revealed any finding that could be attributed to ibuprofen, diphenhydramine, alone or in combination. In the dog studies the maximum tolerated dose was the high dose (16:4 mg/kg/day) of the 13-week study.
Genotoxicity
Ibuprofen has shown no genotoxicity in the in vitro bacterial mutation in the presence and absence of S9 using Salmonella Typhimurium TA1535, TA1538, TA97a, TA100 and TA102. It was also tested in an in vivo sister chromatid exchange assay in the bone marrow of mice dosed orally or intraperitoneal and showed weak genotoxicity in the sister chromatid assay. There was no difference in the occurrence of chromosomal aberrations in cultured human lymphocytes in patients before or after treatment with ibuprofen. A recent study in mouse bone marrow cells suggested a potential for chromosomal aberrations after oral dosing. Overall, it was not genotoxic in vitro but was weakly mutagenic in vivo.
Carcinogenicity
Thirty male and thirty female rats were given 180 mg/kg/day of ibuprofen orally for 55 weeks and 60 mg/kg/day for the next 60 weeks. The only specific pathological effect observed was intestinal ulceration. There was no evidence of tumour induction and it is concluded that ibuprofen is not carcinogenic in the rat.
Reproductive and Developmental Toxicology
Teratology Studies
In the teratology studies in rats and rabbits at the high dose (60:15 mg/kg/day, ibuprofen: diphenhydramine) there were reduced weight gains in both species during the treatment periods, but not during the overall duration of the study. None of the doses, including the high dose, caused any embryotoxic, fetotoxic, or teratogenic effects.
Overall, ibuprofen induced prototypical GI lesions characterized by erosions and ulcers. In addition, many animals at the higher doses showed renal papillary necrosis and/or edema. Rats and dogs are highly sensitive to NSAIDs compared to humans and, therefore, presented with these findings. Diphenhydramine is an antihistaminic drug with sedative properties. Animals given the high doses of this drug showed darkening or reddening of the major organs in the thorax and abdomen. The cause of these findings may result from physiologic depression resulting in decreased blood circulation with stasis occurring in these tissues. Rats who received diphenhydramine in the acute studies usually died within the first day or so after dosing, earlier than rats given ibuprofen. There was no indication of drug:drug interaction in any of the studies with the proposed combination drug product.
Teratology Study in Rabbits
New Zealand white rabbits were given 0, 7.5, 20 and 60 mg/kg daily of ibuprofen from day 1 to day 29 of pregnancy. The mean fetal weight was unaffected; litter size was unaffected at the lower doses. Congenital malformations did occur in both treated and untreated groups with no consistent pattern except for one litter of 4 young with cyclopia. The results of this experiment indicate that ibuprofen is not teratogenic when given in toxic doses to rabbits.
Teratology Study in Rats
Newly-mated female albino rats were given ibuprofen in doses of 0, 7.5, 20, 60 and 180 mg/kg/day from day 1 to day 20 of pregnancy; ibuprofen exhibited no embryotoxic or teratogenic effects even when administered at ulcerogenic doses.
Penetration of Ibuprofen into the Rabbit and Rat Fetus
Rabbits and rats in late pregnancy were given single oral doses of 60 and 20 mg/kg respectively of C14 labelled ibuprofen. Rabbits were killed three hours after dosing and rats killed 1.5 hours after dosing when maternal and fetal blood was collected. Similar concentrations of radioactive ibuprofen were detected in both the mother and fetus indicating that the drug and its metabolites readily crossed the placental barrier into the fetal circulation.