


Product Monograph - Alfacalcidol Capsules
1. INDICATIONS
Alfacalcidol Capsules is indicated in adult patients with chronic renal failure for:
- Management of hypocalcemia
- Secondary hyperparathyroidism
- Osteodystrophy
1.1. Pediatrics
Pediatrics (< 18 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of alfacalcidol capsules in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2. Geriatrics
Geriatrics (> 65 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use (see 7.1.4 Geriatrics).
2. CONTRAINDICATIONS
- Alfacalcidol is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Alfacalcidol is contraindicated when there is biochemical evidence of hypercalcemia, hyperphosphatemia, or evidence of vitamin D overdose.
4. DOSAGE AND ADMINISTRATION
4.1. Dosing Considerations
- Alfacalcidol Capsules has a narrow therapeutic margin, therefore, the optimal daily dose must be carefully individualized and titrated for each individual patient according to such factors as the state of renal function, degree of bone mineralization, and initial plasma calcium and alkaline phosphatase concentrations (see 4.2 Recommended Dose and Dosage Adjustment). Other factors that should be taken into consideration are urinary calcium excretion, plasma parathyroid hormone (PTH) and phosphorus. Laboratory tests considered essential for adequate patient monitoring include serum calcium, inorganic phosphorus, magnesium, alkaline phosphatase, creatinine, BUN and protein (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests
- The success of treatment with Alfacalcidol Capsules is also dependant on the patient receiving an adequate daily intake of calcium during treatment. The recommended daily allowance of calcium in adults is about 800-1000 mg (from all sources such as dialysate, diet and calcium supplements). The treating physician should ensure that each patient receives an adequate daily intake of calcium by prescribing a calcium supplement or instructing the patients in appropriate dietary measures. Calcium supplements should not exceed 500 mg of elemental calcium per day.
- Treatment with Alfacalcidol Capsules may lead to hypercalcemia with its occurrence dependent on such factors as the degree of bone mineralization, the state of renal function, and the dose of Alfacalcidol Capsules. Dosages of Alfacalcidol Capsules in excess of daily requirements can cause hypercalcemia, hypercalciuria, and hyperphosphatemia. Concomitant high intake of calcium and phosphate with therapeutic doses of Alfacalcidol Capsules may also cause similar abnormalities. Regular monitoring of plasma calcium is essential (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
- To prevent hyperphosphatemia and extra-skeletal calcifications, appropriate oral phosphate binding agents in association with a low phosphate diet may be necessary (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism)
- For treatment of hypercalcemia due to overdose, see 5 OVERDOSAGE.
- Chronic hypercalcemia can lead to generalized vascular calcification, nephrocalcinosis, or calcifications of the cornea or other soft tissues (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
- Periodic ophthalmological examinations and radiological evaluation of suspected anatomical regions for early detection of ectopic calcifications are advisable (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
- Prolonged hypercalcemia may aggravate nephrolithiasis and should be avoided when Alfacalcidol Capsules is used in patients with chronic renal failure who have a disposition toward hypercalcemia. Transient or even long-lasting deterioration of kidney function has been observed. In patients with renal bone disease or severely reduced renal function, a phosphate binding agent could be used simultaneously with alfacalcidol to prevent increased serum phosphate and potential metastatic calcification (see 7 WARNINGS AND PRECAUTIONS, Renal). Patients with renal bone disease and a relatively high initial plasma calcium and "autonomous" hyperparathyroidism are liable to early hypercalcemia, as are the minority of dialysis patients with low plasma alkaline phosphatase (see 7 WARNINGS AND PRECAUTIONS, General).
- Prolonged hypercalcemia may aggravate arteriosclerosis or cardiac valve sclerosis and therefore, it should be avoided when Alfacalcidol Capsules is used in patients with these conditions. Alfacalcidol Capsules should also be used with caution in patients with calcification of pulmonary tissue as this may result in cardiac disease (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
- Alfacalcidol Capsules should be used with extreme caution in patients concomitantly using cardiac glycosides. Concurrent use of digitalis glycosides may trigger cardiac arrhythmias in patients with heart disease due to the risk of hypercalcaemia. Calcium levels should be monitored in these patients (see 9.2 Drug Interactions Overview, Drug-Drug Interactions).
- Alfacalcidol Capsules should not be used concomitantly with other vitamin D products or derivatives (see 7 WARNINGS AND PRECAUTIONS, General). Concurrent use of other vitamin D-containing preparations may enhance the risk of hypercalcaemia. The use of multiple vitamin D analogues should be avoided (see 9.2 Drug Interactions Overview, 9.4. Drug-Drug Interactions).
- Concurrent use of Alfacalcidol Capsules with thiazide diuretics or calcium containing preparations may enhance the risk of hypercalcaemia. Calcium levels should be monitored in these patients (see 9.2 Drug Interactions Overview, 9.4 Drug-Drug Interactions).
- Anticonvulsants (e.g. barbiturates, phenytoin, carbamazepine or primidone) have enzyme-inducing effects resulting in an increased metabolism of alfacalcidol. Patients taking anticonvulsants may require larger doses of Alfacalcidol Capsules (see 9.2 Drug Interactions Overview, 9.4 Drug-Drug Interactions).
- Absorption of magnesium-containing antacids may be enhanced by Alfacalcidol Capsules, increasing the risk of hypermagnesemia. The use of magnesium-containing antacids should be avoided (see 9.2 Drug Interactions Overview, 9.4. Drug-Drug Interactions).
- Alfacalcidol Capsules may increase the serum concentration of aluminium. Patients taking aluminium-containing preparations (e.g. aluminium hydroxide, sucralfate) should be monitored for signs of aluminium related toxicities (see 9.2 Drug Interactions Overview, 9.4. Drug-Drug Interactions).
- Mineral oil used as a laxative may interfere with the intestinal absorption of oral Alfacalcidol Capsules formulations. Alfacalcidol Capsules should be administered at least 1 hour before, or 4 to 6 hours after the intake of mineral oil in order to minimize the potential risk of interaction (see 9.2 Drug Interactions Overview, 9.4. Drug-Drug Interactions).
- Concomitant oral administration of bile acid sequestrants such as cholestyramine may impair the intestinal absorption of oral Alfacalcidol Capsules formulations. Alfacalcidol Capsules should be administered at least 1 hour before or 4 to 6 hours after the intake of the bile acid sequestrant in order to minimize the potential risk of interaction (see 9.2 Drug Interactions Overview, 9.4. Drug-Drug Interactions).
- Alfacalcidol Capsules should be used with caution in patients with granulomatous diseases such as sarcoidosis where the sensitivity to vitamin D is increased due to increased hydroxylation activity (see 7 WARNINGS AND PRECAUTIONS, Sensitivity).
Alfacalcidol Capsules should not be used in pregnancy unless clearly necessary, as
hypercalcemia during pregnancy may produce congenital disorders in the offspring. The safety of Alfacalcidol Capsules in pregnant women has not been established (see 7.1.1 Pregnant Woman).
- Breastfeeding during treatment with Alfacalcidol Capsules should be avoided as the drug may be excreted in human milk (see 7.1.2 Breastfeeding).
- Alfacalcidol Capsules is not indicated for and should not be used in pediatric patients less than 18 years of age (see 1.1 Pediatrics). The safety and efficacy of Alfacalcidol Capsules in pediatric patients have not been established (see 7.1.3 Pediatrics).
Alfacalcidol Capsules is not indicated for and should not be used in geriatric patients aged
- 65 years and older (see 1.2 Geriatrics). No data are available for the use of Alfacalcidol Capsules in geriatric patients (see 7.1.4 Geriatrics).
4.2. Recommended Dose and Dosage Adjustment
Alfacalcidol Capsules can be administered once daily with or without food and/or drink.
Pre-Dialysis Patients on Daily Oral Therapy
Dose Titration: A dose of Alfacalcidol Capsules that maintains serum calcium (adjusted for albumin concentration) within the normal range should be selected.
An initial dose of 0.25 mcg/day is recommended for the first 2 months, unless hypercalcemia develops. If hypercalcemia occurs then the dose should be reduced to 0.25 mcg on alternate days. If serum calcium is below the desired range, the dose may be adjusted in increments of 0.25 mcg/day every 2 months.
Maintenance Doses: Most patients will be maintained on a dose of 0.5 mcg/day. However, doses up to 1 mcg/day may be necessary to maintain serum calcium within the desired range.
Serum calcium and phosphate levels should be monitored at monthly intervals or as is considered necessary if hypercalcemia develops. If hypercalcemia develops at any time during treatment then the dose of alfacalcidol should be reduced by 50% and all calcium supplements stopped until calcium levels return to normal.
Dialysis Patients on Daily Oral Therapy
Dose Titration: The recommended initial dose of Alfacalcidol Capsules is 1 mcg/day. If a satisfactory response in the biochemical parameters and clinical manifestations is not observed within 4 weeks, the daily dose may be increased by 0.5 mcg every 2 to 4 weeks. Most patients respond eventually to a dose of between 1 and 2 mcg/day. Only exceptionally, a dose of 3 mcg is required.
During this titration period, serum calcium levels should be obtained at least twice weekly and, if hypercalcemia is noted, the drug should be discontinued immediately until serum calcium levels normalize.
Maintenance Doses: Once serum calcium levels are normalized or only slightly reduced, the dose requirement of Alfacalcidol Capsules generally decreases. Maintenance doses usually range from 0.25 - 1.0 mcg/day. If this small maintenance dose still proves too high, adequate control can usually be achieved by giving the dose on alternative days or even less frequently.
Serum calcium and phosphate levels should be monitored at monthly intervals or as is considered necessary if hypercalcemia develops. If hypercalcemia develops at any time during treatment then the dose of alfacalcidol should be reduced by 50% and all calcium supplements stopped until calcium levels return to normal.
4.4. Administration
Alfacalcidol oral capsules: Should be taken orally as whole capsules and should not be divided. Can be taken with food.
4.5. Missed Dose
If a dose is missed, patients should take the missed dose as soon as possible. However, if it is almost time for the next dose, then patients should not double the dose.
5. OVERDOSAGE
Dosages of Alfacalcidol Capsules in excess of daily requirements can cause hypercalcemia, hypercalciuria and hyperphosphatemia. Conversely, a high intake of calcium and phosphate concomitantly with therapeutic doses of alfacalcidol capsules may cause similar abnormalities.
Treatment of Hypercalcemia Due to Overdose
General treatment of serum calcium levels more than 1 mg/dL or 0.25 mmol/L above the upper limit of the normal range (usually 8.0 - 10.4 mg/dL or 2.2 - 2.6 mmol/L) consists of immediate discontinuation of Alfacalcidol Capsules, institution of a low calcium diet and withdrawal of calcium supplements. Serum calcium levels should be determined daily until the patient achieves normocalcemia. Hypercalcemia frequently resolves in 2 to 7 days. Alfacalcidol Capsules therapy can be re-instituted at half the previous dose when serum calcium levels have returned to within normal limits. Serum calcium levels should be carefully monitored (at least twice weekly) during this period of dosage adjustment and subsequent dosage titration. Persistent or markedly elevated serum calcium levels in hemodialysis patients may be corrected by dialysis against a calcium- free dialysate.
In severe cases of hypercalcemia general supportive measures should be undertaken: Keep the patient well hydrated by IV infusion of saline (force diuresis), measure electrolytes, calcium, and renal functions indices, assess electrocardiographic abnormalities, especially on patients using digitalis glycosides. More specifically, treatment with glucocorticosteroids, loop diuretics, bisphosphonates, calcitonin and eventually hemodialysiswith low calcium contents should be considered.
Treatment of Accidental Overdosage
The treatment of acute accidental overdosage with Alfacalcidol Capsules should consist of general supportive measures. If drug ingestion is discovered within a relatively short time, induction of emesis or gastric lavage may be of benefit in preventing further absorption. If the drug has passed through the stomach, the administration of mineral oil may promote its fecal elimination. Serial serum electrolyte determinations (especially calcium ion), rate of urinary calcium excretion and assessment of electrocardiographic abnormalities due to hypercalcemia should be obtained. Such monitoring is critical in patients receiving digitalis glycosides. Discontinuation of supplemental calcium and low calcium diet are also indicated in accidental overdosage. Due to the relatively short pharmacological action of alfacalcidol Capsules, further measures are probably unnecessary. However, if persistent and markedly elevated serum calcium levels occur, there are a variety of therapeutic alternatives which may be considered depending on the underlying condition of the patient. These include the use of drugs such as phosphates and corticosteroids as well as measures to induce an appropriate forced diuresis. The use of dialysis against a calcium-free dialysate has also been reported.
For management of a suspected drug overdose, contact your regional poison control centre.
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients | Description / Packaging |
|---|---|---|---|
| Oral | Capsules 0.25 mcg alfacalcidol / capsule | Sesame oil and all-rac-α- tocopherol; shell composition: Gelatin [TSE-BSE Free] [COS grade], Glycerol /Glycerin, Potassium Sorbate (Powder) (E 202), Purified water, Titanium dioxide (E171), Medium chain Triglyceride (trace amounts), Sesame oil (trace amounts) and Nitrogen (trace amounts). | Cream-coloured, egg- shaped soft gelatin capsules Available in tropical blisters of 10 (1x10 blisters). |
Capsules 1 mcg alfacalcidol / capsule | Sesame oil and all-rac-α- tocopherol; shell composition: Gelatin [TSE-BSE Free] [COS grade], Glycerol /Glycerin, Potassium Sorbate (Powder) (E 202), Purified water, Ferric oxide (Red) (E172), Ferric oxide (Black) (E172), Titanium dioxide (E171), Medium chain Triglyceride (trace amounts), Sesame oil (trace amounts) and Nitrogen (trace amounts). | Brown egg-shaped soft gelatin capsules. Available in tropical blisters of 10 (1x10 blisters). |
7. WARNINGS AND PRECAUTIONS
General
The therapeutic margin with Alfacalcidol Capsules is narrow, therefore, the optimal daily dose must be carefully titrated for each individual patient (See 4.2 Recommended Dose and Dosage Adjustment).
Alfacalcidol Capsules should not be used concomitantly with other vitamin D products or derivatives.
Alfacalcidol capsules is a potent cholecalciferol derivative with a profound positive effect on intestinal absorption of dietary calcium, which may lead to hypercalcemia. The occurrence of hypercalcemia depends on such factors as the degree of bone mineralization, the state of renal function and the dose of Alfacalcidol Capsules. Excessive doses of the drug induce hypercalcemia and hypercalciuria.
The effect of alfacalcidol capsules on inorganic phosphorus absorption is less marked than its effect on calcium, although it is important to recognize that the drug may increase plasma phosphorus concentrations, which may increase the requirements for phosphate binding agents.
Regular monitoring of plasma calcium is essential. (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests for additional information).
Patients with renal bone disease and a relatively high initial plasma calcium and "autonomous" hyperparathyroidism are liable to early hypercalcemia, as are the minority of dialysis patients with low plasma alkaline phosphatase.
Cardiovascular
Prolonged hypercalcemia may aggravate arteriosclerosis or cardiac valve sclerosis and therefore prolonged hypercalcemia should be avoided when Alfacalcidol Capsules is used in these patients. Alfacalcidol Capsules should also be used with caution in patients with calcification of pulmonary tissue as this may result in cardiac disease.
In patients on digitalis glycosides hypercalcemia may precipitate cardiac arrhythmias. In such patients Alfacalcidol Capsules should be used with extreme caution.
Endocrine and Metabolism
As with all vitamin D preparations and metabolites, hypercalcemia must be anticipated when using Alfacalcidol Capsules.
Chronic hypercalcemia can lead to generalized vascular calcification, nephrocalcinosis or calcifications of the cornea or other soft tissues. During treatment with Alfacalcidol Capsules, the Calcium-Phosphorus Product (Ca X P) (Ca = total serum calcium, mg/dL; P = serum inorganic phosphate, mg/dL) should be maintained at accepted levels. A dialysate calcium level of 1.75 mmoles/L or above, in addition to excess dietary calcium supplements may lead to frequent episodes of hypercalcemia.
To control serum inorganic phosphate levels and dietary phosphate absorption, appropriate oral phosphate binding agents in association with a low phosphate diet may be necessary to prevent hyperphosphatemia and extra-skeletal calcifications. Serum phosphate levels were maintained below 2.0 mmol/L in the study that demonstrated the benefits of daily oral alfacalcidol capsules on the development of bone disease in pre-dialysis patients.
Patients should be informed about the clinical symptoms connected with hypercalcemia. Signs of hypercalcemia are anorexia, fatigue, nausea and vomiting, constipation or diarrhea, polyuria, sweating, headache, polydipsia, hypertension, somnolence and vertigo (see 8 ADVERSE REACTIONS).
Monitoring and Laboratory Tests
Regular monitoring of plasma calcium is essential. Indeed, Alfacalcidol Capsules should only be used when adequate facilities are available for monitoring of blood and urine chemistries on a regular basis. During treatment with Alfacalcidol Capsules, progressive hypercalcemia either due to hyper-responsiveness or overdose may become so severe that it requires emergency treatment. Hypercalcemia can be rapidly corrected by stopping treatment until plasma calcium levels return to normal (in about one week). Alfacalcidol Capsules may then be restarted at a reduced dose (half the previous dose) with monitoring of calcium.
Laboratory tests considered essential to adequate patient monitoring include serum calcium, inorganic phosphorus, magnesium, alkaline phosphatase, creatinine, BUN and protein (for correction of plasma calcium in instances of hypercalcemia). For pre-dialysis patients treated with Alfacalcidol Capsules, serum calcium and phosphate levels should be monitored at monthly intervals or as is considered necessary if hypercalcemia develops. For patients undergoing dialysis serum calcium should be determined at least twice weekly during dose titration. During maintenance therapy with Alfacalcidol Capsules 24-hour urinary calcium and phosphorus should be determined periodically.
Periodic ophthalmological examinations and radiological evaluation of suspected anatomical regions for early detection of ectopic calcifications are advisable.
Renal
The appearance of hypercalcemia is predicated on the ease with which calcium is utilized for bone mineralization and on renal excretion. Thus, chronic renal failure is a condition which would dispose patients toward hypercalcemia.
Prolonged hypercalcemia may aggravate nephrolithiasis and therefore prolonged hypercalcemia should be avoided when Alfacalcidol Capsules is used in these patients. Transient or even long-lasting deterioration of kidney function has been observed.
In patients with renal bone disease or severely reduced renal function, a phosphate binding agent could be used simultaneously with alfacalcidol to prevent increased serum phosphate and potential metastatic calcification.
Reproductive Health: Female and Male Potential
See 7.1.1 Pregnant Woman.
Fertility
No data are available.
Sensitivity
Alfacalcidol Capsules should be used with caution in patients with granulomatous diseases such as sarcoidosis where the sensitivity to vitamin D is increased due to increased hydroxylation activity.
7.1. Special Population
7.1.1. Pregnant Woman
Alfacalcidol Capsules should not be used in pregnancy unless clearly necessary, as hypercalcemia during pregnancy may produce congenital disorders in the offspring. The safety of Alfacalcidol Capsules in pregnant women has not been established.
Studies in animals have shown reproductive toxicity, which include reduced pregnancy rates, litter sizes, and birth weights (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2. Breastfeeding
Alfacalcidol Capsules may be excreted in human milk. Therefore, breast feeding during treatment should be avoided.
7.1.3. Pediatrics
Pediatrics (< 18 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of alfacalcidol capsules in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
A rise in plasma creatinine (or a fall in glomerular filtration rate) has been reported in children with renal failure who are treated with alfacalcidol. However, it is unclear whether this response was due to the action of the drug or to increased creatinine production during growth.
7.1.4 Geriatrics
Geriatrics (> 65 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use (see 1.2 Geriatrics).
8. ADVERSE REACTIONS
8.1. Adverse Reaction Overview
In general, the adverse effects of Alfacalcidol Capsules are similar to those encountered with excessive vitamin D intake.
Adverse reactions as listed by MedDRA system organ class (SOC) are as follows:
Metabolism and nutrition disorders
Elevated blood urea nitrogen (BUN), albuminuria, hypercholesterolemia, elevated aspartate aminotransferase (AST or SGOT) and alanine aminotransferase (ALT or SGPT), anorexia, weight loss, polydipsia, hyperthermia, dry mouth, metallic taste
Cardiac disorders
Cardiac arrhythmia, hypertension
Eye disorders
Conjunctivitis, corneal calcification, photophobia
Infections and Infestations
Rhinorrhea
Psychiatric disorders
Overt psychosis
Nervous system disorders
Headache, somnolence, vertigo
Gastrointestinal disorders
Diarrhea, vomiting, constipation, nausea, pancreatitis
Skin and subcutaneous tissue disorders
Pruritus
Musculoskeletal and connective tissue disorders
Muscle pain, bone pain, ectopic calcification
Renal and urinary disorders
Polyuria, nocturia
Reproductive system and breast disorders
Decreased libido
General disorders and administration site conditions
Fatigue, weakness
8.2. Clinical Trial Adverse Reactions
This information is not available for this drug product.
8.3. Less Common Clinical Trial Adverse Reactions
This information is not available for this drug product.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
This information is not available for this drug product.
8.5. Post-Market Adverse Reactions
Hypercalcemia and possibly an exacerbation of hyperphosphatemia are the more frequent adverse reactions that have been reported with alfacalcidol capsules in patients with renal osteodystrophy. Elevated levels of calcium and phosphorus increase the risk of metastatic calcification and may accelerate the decline in renal function in some patients with chronic renal failure.
Metabolism and nutrition disorders: hypercalcaemia, hypercalciuria, hyperphosphatemia
Skin: rash
Gastrointestinal: abdominal pain, loss of appetite
Renal and urinary disorders: renal failure, kidney stones
9. DRUG INTERACTIONS
9.2. Drug Interactions Overview
Cardiac glycosides
Concurrent use of digitalis glycosides may trigger cardiac arrhythmias in patients with heart disease due to the risk of hypercalcaemia. Calcium levels should be monitored.
Thiazide diuretics and calcium containing preparations
Concurrent use of thiazide diuretics or calcium containing preparations may enhance the risk of hypercalcaemia. Calcium levels should be monitored.
Other vitamin D-containing preparations
Concurrent use of other vitamin D-containing preparations may enhance the risk of hypercalcaemia. Use of multiple vitamin D analogues should be avoided.
Anticonvulsants
Anticonvulsants (e.g. barbiturates, phenytoin, carbamazepine or primidone) have enzyme- inducing effects resulting in an increased metabolism of alfacalcidol. Patients taking anticonvulsants may require larger doses of Alfacalcidol Capsules.
Magnesium-containing antacids
Absorption of magnesium-containing antacids may be enhanced by Alfacalcidol Capsules, increasing the risk of hypermagnesemia. Magnesium-containing antacids should be avoided.
Aluminium-containing preparations
Alfacalcidol Capsules may increase the serum concentration of aluminium. Patients taking aluminium- containing preparations (e.g. aluminium hydroxide, sucralfate) should be monitored for signs of aluminium related toxicities.
Mineral oil laxatives
Mineral oil used as a laxative may interfere with the intestinal absorption of oral Alfacalcidol Capsules formulations. Alfacalcidol Capsules should be administered at least 1 hour before, or 4 to 6 hours after the intake of mineral oil in order to minimize the potential risk of interaction.
Bile acid sequestrants
Concomitant oral administration of bile acid sequestrants such as cholestyramine may impair the intestinal absorption of oral Alfacalcidol Capsules formulations. Alfacalcidol Capsules should be administered at least 1 hour before or 4 to 6 hours after the intake of the bile acid sequestrant in order to minimize the potential risk of interaction.
9.3. Drug-Behavioural Interactions
No potential interactions in terms of individual behaviour are known. The patients should follow the recommendations given in the patient medication information or by health professionals.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Effect | Clinical comment |
|---|---|---|
| Digitalis glycosides | Hypercalcemia may trigger cardiac arrhythmias | Calcium levels should be monitored |
| Mineral oil used as a laxative | May interfere with the intestinal absorption of Alfacalcidol Capsules | Alfacalcidol Capsules should be administered at least 1 hour before, or 4 to 6 hours after the intake of mineral oil in order to minimize the potential risk of interaction |
Thiazide diuretics or Calcium containing preparations | May enhance the risk of hypercalcemia | Calcium levels should be monitored. |
| Vitamin D | May enhance the risk of hypercalcaemia | Use of multiple concurrent vitamin D analogues should be avoided. |
Anticonvulsants (e.g., barbiturates, phenytoin, carbamazepine or primidone) | Have enzyme-inducing effects resulting in an increased metabolism of alfacalcidol | Patients taking anticonvulsants may require larger doses of Alfacalcidol Capsules |
| Antacids containing magnesium | May contribute towards hypermagnesemia | Should be avoided |
| Aluminium containing preparations (e.g., aluminium hydroxide, sucralfate) | Alfacalcidol Capsules may increase the serum concentration of aluminium | Patients should be monitored for signs of aluminium related toxicities |
| Bile acid sequestrants such as cholestyramine | Oral administration may impair the intestinal absorption of oral Alfacalcidol Capsules formulations | Alfacalcidol Capsules should be administered at least 1 hour before, or 4 to 6 hours after the intake of the bile acid sequestrant in order to minimize the potential risk of interaction |
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. CLINICAL PHARMACOLOGY
10.1. Mechanism of Action
Alfacalcidol stimulates intestinal calcium and phosphorus absorption, the reabsorption of calcium from bone and possibly the renal reabsorption of calcium.
10.2. Pharmacodynamics
In the majority of patients treated with alfacalcidol capsules, clinical symptoms of bone pain and muscle weakness begin to remit within 2 weeks to 3 months of the start of therapy. Malabsorption of calcium is rapidly corrected. In patients on daily oral therapy, plasma alkaline phosphatase and PTH levels generally begin to fall within 3 months, but plasma calcium levels may not normalize for several months. This delay should not necessarily be construed as a poor response but may indicate that calcium is being utilized for bone mineralization.
Hypercalcemia may occur at any stage of treatment, the risk being higher just after treatment is started and later when the plasma alkaline phosphatase level falls towards normal (See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Because of a modest action on intestinal phosphorus absorption, Alfacalcidol Capsules may elevate plasma phosphorus levels even further in patients with renal osteodystrophy and this may require increasing the dose of phosphate binding agents.
Normalization of plasma PTH levels frequently correlates well with healing of osteitis fibrosa, but radiographic improvement can occur without significant changes in plasma PTH concentrations. After 3 to 6 months of treatment, radiological evidence of healing is generally apparent. Histological responses, such as a decrease in the surface of bone undergoing resorption and a decrease in the volume of osteoid, are often much slower.
10.3. Pharmacokinetics
Absorption:
The biological half-life of alfacalcidol has been shown to be approximately 3 hours in the presence of renal insufficiency. However, serum levels of its active metabolite calcitriol peak approximately 12 hours after a single dose of oral Alfacalcidol Capsules. Levels of calcitriol remain measurable for at least 48 hours. The effect of 1 mcg of oral Alfacalcidol Capsules on intestinal calcium absorption has been observed within 6 hours of ingestion and was maximal at 24 hours.
Distribution:
There is evidence that vitamin D, its 1α-hydroxylated metabolites and analogues are extensively bound to a serum binding protein of the α -globulin fraction. Calcitriol appears to function in the intestine and bone by a receptor-nuclear activation mechanism.
Metabolism:
Vitamin D is itself biologically inactive and only expresses its physiological effects after undergoing two metabolic conversions. Before any physiological action can take place, vitamin D must first be hydroxylated at the 25 position in the liver to the metabolic intermediary 25- OHD3. Secondly, 25-OHD3 undergoes a 1α-hydroxylation in the kidney to the physiologically active metabolite 1,25-(OH)2D3, referred to as calcitriol or 1,25-dihydroxy-vitamin D3.
In contrast to Vitamin D, alfacalcidol is converted to calcitriol in the liver, effectively bypassing the critical renal metabolic conversion. This hepatic conversion of Alfacalcidol Capsules is accomplished very rapidly, before any stimulation of the intestine or bone occurs. Impairment of the hepatic conversion of alfacalcidol to calcitriol is rare, even in the presence of liver abnormalities.
Elimination
No data are available.
Special Populations and Conditions
Geriatrics
Health Canada has not authorized an indication for geriatric use.
- Pediatrics
Health Canada has not authorized an indication for pediatric use.Renal Insufficiency:
Conversion of 25-OHD3 to calcitriol in the kidney becomes impaired or blocked-in patients with renal failure or disorders of calcium and phosphorus metabolism. These patients respond poorly to even high doses of vitamin D. Hypocalcemia may lead to increased PTH secretion and high plasma PTH levels. Therefore, the patients with renal bone disease most likely to benefit from Alfacalcidol Capsules therapy are those characterized by abnormally low plasma calcium levels, elevated alkaline phosphatase and PTH levels, and histological evidence of osteitis fibrosa and osteomalacia.
- STORAGE, STABILITY AND DISPOSAL
0.25 mcg soft gel Capsules: Protect from direct sunlight. Store at 25 ± 2°C.
1 mcg soft gel Capsules: Protect from direct sunlight. Store at 25 ± 2°C.
- 12. SPECIAL HANDLING INSTRUCTIONS
No special requirements for handling.
PART II: SCIENTIFIC INFORMATION
- 13. PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Alfacalcidol
(1α-hydroxyvitamin D3 1α- hydroxycholecalciferol, 1α-hydroxyvitamin D3, 1α-OHD3)
Chemical Name: (5Z, 7E)-9,10-secocholesta-5,7,10(19)-triene-1α, 3β-diol Molecular Formula: C27H44O2
Molecular Mass: 400.6
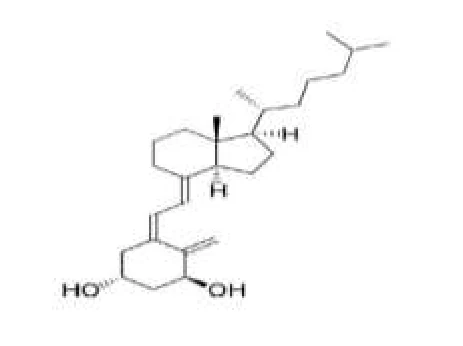
Structural Formula:
Physicochemical Properties: Alfacalcidol is a colorless crystalline compound with a melting range of 136o-144oC. It is sensitive to light and very soluble in methanol, ethanol and chloroform, soluble in ether, sparingly soluble in methylformate and acetonitrile.
14. CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Pivotal Study:
The beneficial effects of alfacalcidol capsules on the development of renal bone disease in pre-dialysis patients have been demonstrated in a large, randomized, placebo-controlled study. Long-term administration of alfacalcidol capsules (maximum dose of 1 mcg/day for up to 2 years) has been performed.
Non-Pivotal Studies
Study 1: Patients with renal failure were treated with 1-5 mcg/day of alfacalcidol.
Study 2: Patients with chronic renal failure received oral alfacalcidol in a dose of 0.5-1.0 mcg/day.
Study 3: In patients with nutritional osteomalacia, effects of 1 mcg oral alfacalcidol have been studied.
14.2. Study Results
Pivotal study
Long-term administration of alfacalcidol capsules improved bone histology and halted the progression of changes in serum alkaline phosphatase activity and parathyroid hormone levels compared to placebo. Long-term administration of alfacalcidol proved to be well tolerated and had no adverse effect on renal function in patients for whom the dose was titrated to prevent persistent hypercalcemia. Although elevation of serum calcium was observed, marked hypercalcemia (> 3.00 mmol/L) was uncommon (4.5% of patients) and readily responded to decreases in drug dosage.
None-Pivotal Studies:
Study 1: In patients with renal failure, 1-5 mcg/day alfacalcidol increased intestinal calcium and phosphorus absorption in a dose-related manner. This effect was observed within 3 days of starting the drug and conversely, it was reversed within 3 days of its discontinuation.
Study 2: The patients have shown increased serum calcium levels within 5 days . Serum calcium levels also increase during the first 4 weeks of treatment with intermittent (2-3 times weekly) intravenous alfacalcidol in a dose of 2.7-8.5 mcg/week. As serum calcium rose, PTH levels and alkaline phosphatase decreased toward normal.
Study 3: In patients with nutritional osteomalacia, increases in calcium absorption were noted within 6 hours of giving 1 mcg alfacalcidol orally and usually peaked at 24 hours. Alfacalcidol also produced increases in plasma inorganic phosphorus due to increased intestinal absorption and renal tubular reabsorption. This latter effect is a result of PTH suppression by alfacalcidol. The effect of the drug on calcium was about double its effect on phosphorus absorption.
14.3. Comparative Bioavailability Studies
This information is not available for this drug product.
14.4. Immunogenicity
This information is not available for this drug product.
15. MICROBIOLOGY
No microbiological information is required for this drug product.
16. NON-CLINICAL TOXICOLOGY
General Toxicology:
In normal and anephric rats given 6.25 - 62500 pmol alfacalcidol and in the chick treated with 0.3-0.6 nmol alfacalcidol, the stimulation of intestinal calcium transport and bone mobilization was between one-half and equal to that of calcitriol. In both species, the conversion of alfacalcidol to calcitriol has been demonstrated by the isolation of radioactive calcitriol after administration of labelled alfacalcidol. Further studies on the transformation have demonstrated 25-hydroxylation in the liver homogenates from both the rat and the chick and also in intestinal mucosa from the chick. Whereas the hepatic 25-hydroxylation of vitamin D3 is feedback regulated, the corresponding conversion of alfacalcidol to calcitriol seems to be quantitative.
The 25-hydroxylation of alfacalcidol in the liver occurs very rapidly. Vitamin D-deficient rats were dosed with the radio-labelled compound (a single dose of 0.125 mcg 1α-OH(6-3H)D3 orally. The intestinal calcium transport in orally dosed animals was noted after 4 hours and reached a maximum at 12 hours. Following both routes, a high level of transport was maintained for up to 96 hours. Intestinal tissue concentrations of 1,25-(OH)2 (6-3H)D3 appeared rapidly, within 2 hours of oral dose of 1α-OH(6-3H)D3. These concentrations maximized by 4 hours at 310 pg/g following the oral dose..
Blood levels and intestinal absorption of both alfacalcidol and calcitriol have also been determined in chicks following the oral. administration of 0.125 mcg 1α-OH(6-3H)D3 . In orally dosed animals, no 1,25-(OH)2 (6-3H)D3 was measured at 1 hour, but at 4 hours the maximum concentration of 1.5 ng/g was reached. These studies demonstrate that the transformation of alfacalcidol to calcitriol occurs rapidly enough to account for the biological response to alfacalcidol. Although it cannot be excluded that alfacalcidol may have a direct effect on the intestine when present at a relatively high concentration immediately after oral administration, it seems reasonable to conclude that it functions mainly after conversion to calcitriol.
Apart from these effects, alfacalcidol appears devoid of pharmacological action.
Acute Toxicity
Studies performed in mice and rats have revealed that alfacalcidol has an acute toxicity which is relatively low as compared to therapeutic doses. The following table illustrates the LD50 values obtained with both species: the discrepancy in the LD50 values reported by two centres are probably attributable to differences in the procedures followed in the two laboratories.
Mice died from 3 to 7 days after dosing by both routes of administration as a result of general calcification.
Rats treated orally with the drug showed progressive general deterioration and were highly emaciated at death. Autopsy revealed general calcification which was most pronounced in the kidneys.
Table 3. LD Values Obtained with 1α-Hydroxyvitamin D3
| SPECIES | ROUTE OF ADMINISTRATION | LD50 (mcg/kg) |
|---|---|---|
| Mice | Oral | 490 |
| Mice (Male) | Oral | 476 |
| Mice (Female) | Oral | 440 |
| Mice | I.V. | 290 |
| Mice (Male) | I.V. | 71 |
| Mice (Female) | I.V. | 56 |
| Rats | Oral | 510 |
|---|---|---|
| Rats (Male | Oral | 340 |
Oral Subacute Toxicity
One study in rats showed that repeated dosing with up to 2.5 mcg/kg/day for 30 days did not cause any untoward effects. Higher doses resulted in hypercalcemia and metastatic calcification.
In another study, rats were dosed with 0.4, 2.0 and 10 mcg/kg/day of the drug for 7-8 weeks. From week 3 onwards, the animals showed signs of general deterioration, apathy and weight loss. Post-mortem examinations revealed a lighter colour and calcinosis in the kidneys in the highest dose group. In the other groups, there was a slight but dose-related calcinosis in the kidneys which was more pronounced in the females than in the males.
Dogs were treated orally for 3 to 8 weeks with alfacalcidol in doses of 0.1, 0.4 and 3.2 mcg/kg/day. After 3 and 7 weeks respectively, dogs on the 3.2 mcg dose and dogs on the 0.4 mcg dose showed considerable deterioration with loss of appetite and weight, apathy and subnormal temperature. Post-mortems revealed slight muscular dehydration and reduced fat deposition. Females on 0.4 mcg/kg/day had scattered small foci of calcium deposits and groups of dilated tubules in the cortex and medulla; the male animals, however, showed only traces of calcium deposition. In all 4 dogs on the highest dose, focal groups of dilated tubules with flattened epithelium and interstitial fibrosis in the cortex and medulla of the kidney were observed. Scattered calcium deposits were present in the fundus of the stomach (mucosa and submucosa) and in the bronchi and alveoli and corresponding vessels. In the group of dogs (2 male and 2 female) treated with 0.1 mcg/kg, histopathology showed one case of calcium deposits in the renal medulla. No other untoward effects were noted in the low dose group.
Intravenous Subacute Toxicity
In a 6 week study in rats dosed with 0.1, 0.3 and 0.9 mcg/kg/d of alfacalcidol, the only dose- effect relationship observed was for hemoglobinuria. Animals in the highest dose group exhibited cessation of growth followed by slight weight loss, languid behaviour, moderate reductions in food consumption, hypothermia, and pale mucous membranes. Pigmented corneal granulations were evident and post-mortem examinations showed weight reductions for the pituitary, ovaries and uterus. Renal tubule casts were also present and there was an increase in the intensity of renal microcalculi in females. In the control group receiving vehicle injections, there was slight hyperuremia and small increases in hemoglobinuria.
Sensitivity to vehicle injections was also noted in a 14 day tolerance study in beagle dogs. Dogs receiving high doses of vehicle (0.4 ml/kg) showed a slight degree of hemolysis immediately after injection which disappeared within 4 hours. In a 6 week study in dogs dosed with 0.01, 0.03, 0.09, and 0.18 mcg/kg/day of alfacalcidol, effects were noted only in the highest dose group. Aside from increases in monocyte number, post-mortem examinations showed vascular calcification and dystrophic mineralization in the aorta and stomach. Kidneys had a firmer texture, the kidney cortex zone had a paler colour, tubules were dilated and had chronic inflammatory cell infiltration.
Chronic Toxicity
Rats were dosed orally with 0.2, 0.8 and 3.2 mcg/kg/day with alfacalcidol for 6 months. Increased serum levels of calcium were recorded in all groups from week 9 onwards; phosphate levels were increased in week 26 and there was a decrease in total protein with the two highest dose levels at the end of the study. Autopsy revealed soft tissue calcification in the kidneys, stomach and aorta with the intermediate and high dose levels. A slight increase in the incidence of calcinosis of the kidney was observed in the low dose group.
In a 6-month study in dogs, the initial oral doses of alfacalcidol were 0.05, 0.1 and 0.2 mcg/kg/day, but because of adverse effects on bodyweight and food consumption, dosing with
0.2 mcg/kg/day was stopped after 72 days. In some of these animals, dosing continued at 0.025 mcg/kg/day which allowed the animals to recover. Apart from the effects with the 0.2 mcg dose, there were no untoward clinical signs or effects on bodyweight or food consumption. The only macroscopic abnormality noted was enlarged spleens in the treated dogs. Two dogs which were sacrificed after the 0.2 mcg/kg dose and 2 other dogs on 0.1 mcg/kg showed areas of dilated basophilic tubules in the kidneys. One dog on 0.2 mcg/kg had numerous calcified foci in the lamina propria of the fundus and excessive muscle stiffness due to soft tissue calcification. Soft tissue calcification was also noted in a dog treated with 0.1 mcg/kg/day.
Reproductive and Developmental Toxicology:
Teratogenic Studies
Studies were performed in rats and rabbits using daily doses of 0.1, 0.3 and 0.9 mcg/kg of alfacalcidol. Parent animals dosed with the drug had a lower weight gain than undosed animals. Reduced litter size and lower weights of fetuses were recorded in rabbits at the intermediate and high dose levels, but no significant increase in the incidence of fetal malformations were noted.
The effect of alfacalcidol on the reproductive function in the rats was investigated using the same doses. At the highest dose level, the pregnancy rate, litter size and birth weights were significantly lower than in control animals, in both the original parent animals and offspring of the first generation. No other parameters were affected and no late effects of the drug were observed in any of the progeny.
17. SUPPORTING PRODUCT MONOGRAPHS
- 1. ONE-ALPHA® Capsules 1 and 0.25 mcg, oral Submission Control Number. 251287, Product Monograph, CHEPLAPHARM Arzneimittel GmbH. date of revision January 26 2022.