


Product Monograph - Andembry
Recent Major Label Changes
| 7 Warnings and Precautions, Hypersensitivity | 2026-10 |
|---|
Table of Contents
Recent Major Label Changes ............................................................................................... 2
Table of Contents ............................................................................................................... 2
Part I: Healthcare Professional Information ........................................................................ 4
- 1.
Indications .............................................................................................................. 4
1.1. Pediatrics .......................................................................................................... 4
1.2. Geriatrics .......................................................................................................... 4
- 2. Contraindications .................................................................................................... 4
- 4.
Dosage and Administration ..................................................................................... 4
4.1. Dosing Considerations ...................................................................................... 4
4.2. Recommended Dose and Dosage Adjustment ................................................. 4
4.4. Administration .................................................................................................. 5
4.5. Missed Dose ..................................................................................................... 6
- 5. Overdose................................................................................................................. 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ........................................... 7
- 7.
Warnings and Precautions ....................................................................................... 7
General ......................................................................................................................... 7
Reproductive Health .................................................................................................... 8
Sensitivity/Resistance ................................................................................................... 8
7.1. Special Populations ........................................................................................... 8
7.1.1 Pregnancy ......................................................................................................... 8
7.1.2 Breastfeeding ................................................................................................... 8
7.1.3 Pediatrics .......................................................................................................... 8
7.1.4 Geriatrics .......................................................................................................... 9
- 8.
Adverse Reactions ................................................................................................... 9
8.1. Adverse Reaction Overview .............................................................................. 9
8.2. Clinical Trial Adverse Reactions ........................................................................ 9
8.3. Clinical Trial Adverse Reactions – Pediatrics ................................................... 10
8.5. Post-Market Adverse Reactions ..................................................................... 10
- 9.
Drug Interactions .................................................................................................. 10
9.2. Drug Interactions Overview ............................................................................ 10
9.3. Drug-Behaviour Interactions .......................................................................... 10
9.4. Drug-Drug Interactions ................................................................................... 10
9.5. Drug-Food Interactions ................................................................................... 10
9.6. Drug-Herb Interactions ................................................................................... 10
9.7. Drug-Laboratory Test Interactions .................................................................. 11
- 10.
Clinical Pharmacology ........................................................................................... 11
10.1. Mechanism of Action ...................................................................................... 11
10.2. Pharmacodynamics ........................................................................................ 11
10.3. Pharmacokinetics ........................................................................................... 11
10.4. Immunogenicity .............................................................................................. 13
- 11. Storage, Stability, and Disposal ............................................................................. 14
- 12. Special Handling Instructions ................................................................................ 14
Part 2: Scientific Information ............................................................................................ 15
- 13. Pharmaceutical Information .................................................................................. 15
- 14.
Clinical Trials ......................................................................................................... 15
14.1. Clinical Trials by Indication ............................................................................. 15
- 16. Non-Clinical Toxicology ......................................................................................... 18
Patient Medication Information ....................................................................................... 19
Part I: Healthcare Professional Information
1. Indications
ANDEMBRY (garadacimab injection) is indicated for routine prevention of attacks of hereditary angioedema (HAE) in adult and pediatric patients (aged 12 years and older).
ANDEMBRY is not intended for acute treatment of HAE attacks.
1.1. Pediatrics
Adolescents (≥ 12 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ANDEMBRY in pediatric patients age 12 years and older has been established. Therefore, Health Canada has authorized an indication for pediatric use above 12 years age group (see 4 Dosage and Administration, Recommended Dose and Dosage Adjustment).
Pediatrics (<12 years): The safety and efficacy of ANDEMBRY in pediatric patients below the age of 12 have not been established.
1.2. Geriatrics
The safety and efficacy of ANDEMBRY were evaluated in two phase 3 studies with patients (N=13) aged 65 years of age or older with HAE (see 7.1.4 Geriatrics). No overall differences in safety or efficacy were observed compared to patients 18 to 65 years of age.
2. Contraindications
ANDEMBRY is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container.
For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
This medicinal product should be initiated under the supervision of a healthcare professional experienced in the management of patients with HAE.
4.2. Recommended Dose and Dosage Adjustment
The recommended dose of ANDEMBRY is an initial loading dose of 400 mg administered subcutaneously as two 200 mg injections on the first day of treatment followed by a monthly dose of 200 mg.
Special Populations
Pediatric population
The dosing for pediatric population age 12 and older is same as adults and no dose adjustment is required.
Health Canada has not authorized an indication for children aged less than 12 years.
Geriatric population
The safety and efficacy of garadacimab is not expected to be affected by age. No dose adjustment is required for patients above 65 years of age (see 10 Clinical Pharmacology, Pharmacokinetics).
Hepatic impairment
No studies have been conducted in patients with hepatic impairment. Based on population pharmacokinetic analysis, hepatic impairment is not expected to affect exposure to garadacimab. No dose adjustment is required in patients with hepatic impairment (see 10 Clinical Pharmacology, Pharmacokinetics).
Renal impairment
No studies have been conducted in patients with renal impairment. Based on population pharmacokinetic analysis, renal impairment is not expected to affect exposure to garadacimab. No dose adjustment is required in patients with renal impairment (see 10 Clinical Pharmacology, Pharmacokinetics).
4.4. Administration
- ANDEMBRY is intended for subcutaneous administration only.
- Each ANDEMBRY unit (prefilled syringe with needle safety device (Figure 1) or prefilled pen (Figure 2)) is intended for single use only and is provided as a ready-to-use solution .
- The injection should be restricted to the recommended injection sites: the abdomen, the thighs, and the upper outer arms (see Patient Medication Information - Instruction for Use: step by step guide, Figure E for prefilled pen or Figure F for prefilled syringe). Rotation of the injection site is recommended.
- ANDEMBRY may be self-administered or administered by a caregiver only after training on subcutaneous injection technique by a healthcare professional.
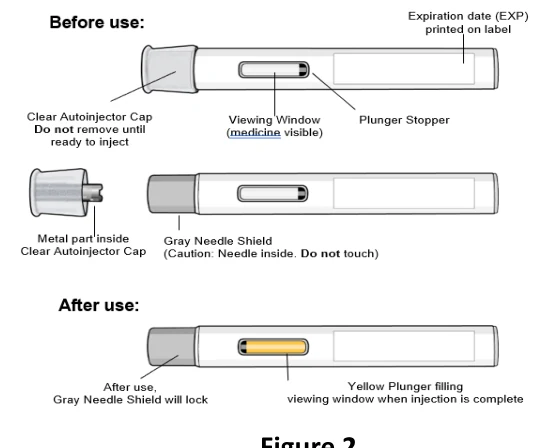
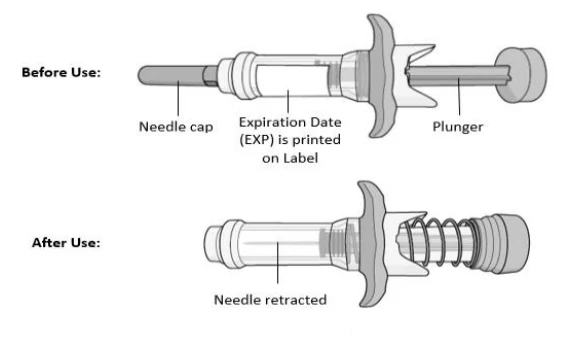
Figure 1
Figure 2
Instruction for Prefilled pen/Prefilled syringe
Assemble Supplies
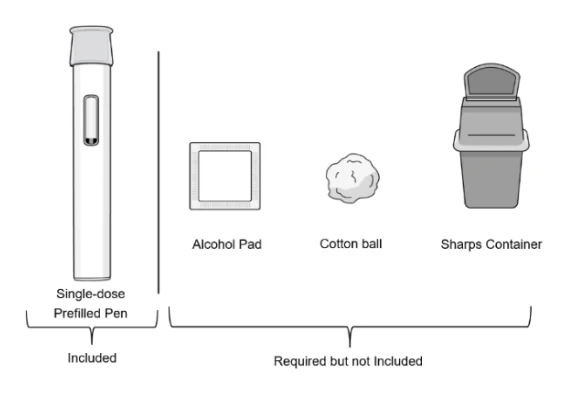
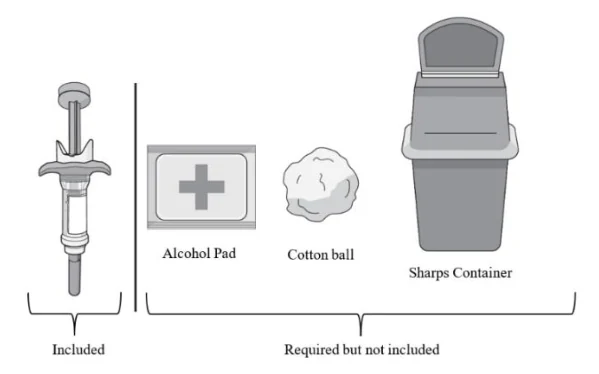
Supplies needed for the Prefilled pen (see Figure 3)/Prefilled syringe (see Figure 4)
Included in the carton box:
- 1 Single-dose Prefilled pen or 1 Prefilled syringe
Required supplies but not included in the carton box:
- 1 Alcohol pad
- 1 Cotton ball or gauze pad
- 1 sharps container or puncture-resistant container for disposal (see Patient Medication Information - Instruction for Use: step by step guide Step 11. Disposing of the Prefilled Pen or Step 12. Disposing of the Syringe)
For detailed instructions on the preparation and administration of ANDEMBRY see Patient Medication Information.
4.5. Missed Dose
If a dose of ANDEMBRY is missed, administer the dose as soon as possible, and then administer the next dose according to the original schedule. If you're unsure about when to take the missed dose, especially if it's close to the time for your next scheduled dose, consult your healthcare professional.
5. Overdose
No cases of overdose were reported in clinical studies. There is no available information to identify potential signs and symptoms of overdose.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
Figure 3
Figure 4
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, including biosimilars, healthcare professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Description
ANDEMBRY is supplied as a sterile, preservative-free solution for subcutaneous administration in the following two presentations.
- 200 mg/1.2 mL solution in a single-dose prefilled glass syringe with needle safety device (Figure 1) or
- 200 mg/1.2 mL solution in a single-dose prefilled pen (Figure 2)
ANDEMBRY is supplied as a sterile, preservative-free solution for subcutaneous administration. ANDEMBRY is supplied as either a single-dose prefilled pen or as a single-dose 1.2 mL prefilled glass syringe with needle safety device. Enclosed within the prefilled pen is a single-dose 1.2 mL prefilled glass syringe. The solution of ANDEMBRY is slightly opalescent to clear, brownish-yellow to yellow liquid, with a pH of approximately 6.1. The solution has an osmolality of approximately 470 mOsm/kg.
Each 1.2 mL prefilled glass syringe delivers 1.2 mL (200 mg) of garadacimab. Each of these contain as nominal quantity per prefilled glass syringe: garadacimab (200 mg), L-arginine monohydrochloride (37.9 mg), L-histidine (3.7 mg), L-proline (19.3 mg), polysorbate 80 (0.24 mg), and water for injection, USP.
7. Warnings and Precautions
General
Acute HAE attacks
ANDEMBRY is not intended for treatment of acute HAE attacks. In case of breakthrough HAE attack, individualised treatment should be initiated with an approved rescue medicine.
Normal C1-INH HAE (nC1-INH)
Some subcategories of normal C1-INH HAE (nC1-INH) may not respond to treatment with garadacimab due to alternative pathways that do not include FXII activation. It is recommended to perform genetic testing, if available, according to the current HAE guidelines. Consideration should be given to discontinuing treatment in patients with nC1-INH who have shown insufficient reduction in attacks after 3 months of treatment.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Subcutaneous administration | Solution for injection, 200 mg / 1.2 mL | L-arginine monohydrochloride, L-histidine, L-proline, Polysorbate 80, Water for injection |
Coagulation disorders & thromboembolism
ANDEMBRY has not been studied in patients with clinically significant bleeding due to coagulopathy or with thromboembolism. There were no garadacimab-related bleeding and thromboembolic events in the clinical studies.
Interference with coagulation test
ANDEMBRY can prolong activated partial thromboplastin time (aPTT) due to an interaction of garadacimab with the aPTT assay (see 9.7 Drug-Laboratory Test Interactions).
Reproductive Health
- Fertility
Effect on fertility has not been evaluated in humans.
Sensitivity/Resistance
Hypersensitivity
Hypersensitivity reactions have been reported post-marketing. The signs and symptoms of hypersensitivity reactions may include hives (local and generalized), tightness of the chest, difficulty breathing, wheezing, hypotension, and/or anaphylaxis during or after injection of ANDEMBRY. In case of severe hypersensitivity reactions, including anaphylaxis, discontinue ANDEMBRY administration and institute appropriate treatment.
7.1. Special Populations
7.1.1. Pregnancy
There are no studies with ANDEMBRY in pregnant women. The extent of exposure in pregnancy during clinical trials was very limited. As a precautionary measure, it is preferable to avoid the use of garadacimab during pregnancy.
A pre- and postnatal development study conducted in pregnant rabbits administered subcutaneous doses of garadacimab resulted in confirmed exposure to the developing fetus. At parturition, fetal plasma garadacimab concentrations can exceed maternal plasma concentrations (see 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology).
7.1.2. Breastfeeding
It is unknown whether ANDEMBRY is excreted in human milk. Human IgGs are known to be excreted in breast milk during the first few days after birth, and decrease to low concentrations soon afterwards. Because human IgGs are known to be excreted in human milk, precaution should be exercised. A risk to the breast-fed child cannot be excluded.
7.1.3. Pediatrics
Adolescents (≥12 years): The safety and efficacy of ANDEMBRY have been established in pediatric patients with HAE aged 12 years and older. The use of ANDEMBRY for this indication was evaluated in 11 pediatric patients (>12 to 17 years) in phase 3 studies. Efficacy and safety results in adolescents were similar to the adult population.
Pediatrics (<12 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use under the age of 12.
7.1.4. Geriatrics
The safety and efficacy of ANDEMBRY were evaluated in two phase 3 studies with patients (N=13) aged 65 years of age or older with HAE. No overall differences in safety or efficacy were observed compared to patients 18 to 65 years of age.
8. Adverse Reactions
8.1. Adverse Reaction Overview
One hundred and sixty-six (166) unique subjects with HAE were exposed to at least one dose of ANDEMBRY 200 mg in one (1) Phase 2 and two (2) Phase 3 clinical trials. The most commonly observed adverse reactions from pooled data from these 3 trials associated with ANDEMBRY were injection site erythema (7.8%), injection site bruising (1.8%), injection site pruritus (3.6%), injection site urticaria (1.2%), headache (11.4%), and abdominal pain (6.6%).
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety of ANDEMBRY is primarily based on a 6-month, randomized, double-blind, parallel-group and placebo-controlled study (Trial 1) in 64 adult and pediatric patients (aged 12 years and older) with Type I or II HAE (see 14 Clinical Trials). A total of 39 patients with HAE aged 12 years and older received at least one dose of ANDEMBRY. Overall, 59.4% of patients were female and 85.9% of patients were Caucasian with a mean age of 41.2 years.
Table 2 below summarizes treatment-emergent adverse events (TEAEs) in ≥5% of patients treated with ANDEMBRY.
Table 2 – Treatment-emergent adverse events (TEAEs) in ≥5% of patients treated with ANDEMBRY (garadacimab) in Trial 1
| System organ class/preferred term | Garadacimab 200 mg (N = 39) n (%) E | Placebo (N = 25) n (%) E |
|---|---|---|
| Any TEAE | 25 (64.1) 75 | 15 (60.0) 54 |
| Infection and infestation | ||
| Upper respiratory tract infection | 4 (10.3) 4 | 2 (8.0) 2 |
| Nasopharyngitis | 3 (7.7) 3 | 1 (4.0) 1 |
| Nervous system disorders | ||
| Headache | 3 (7.7) 9 | 4 (16.0) 4 |
n = number of patients with at least one event; E = number of events
Safety data from all patients treated with ANDEMBRY in a phase 3 open-label extension study with a median exposure of 13.8 months were consistent with data in Table 2.
Description of selected adverse reactions
Injection site reactions
In Trial 1, 3 incidents of injection site reactions of mild severity were observed in 2 (5.1%) patients who received ANDEMBRY. Temporal relationship (began within 1-3 days after investigational product administration) was identified for all three injection site reactions. All three injection site reactions were assessed as related to ANDEMBRY.
In a Phase 3 open-label extension study (Trial 2), 161 patients with HAE were administered ANDEMBRY 200 mg subcutaneously every month; 57 patients had rolled over from Trial 1. Injection site reactions (e.g., injection site bruising, injection site erythema, injection site haematoma, injection site pruritus, injection site urticaria) were reported in 16 (10%) patients.
8.3. Clinical Trial Adverse Reactions – Pediatrics
While limited, the safety profile in pediatric patients 12 years of age and older (n=6) was similar to that of the adult population.
8.5. Post-Market Adverse Reactions
Because postmarketing reports are voluntary and from a population of unknown size, an estimate to the frequency cannot be made.
The following adverse reaction has been identified during post-marketing use of ANDEMBRY.
- Hypersensitivity
9. Drug Interactions
9.2. Drug Interactions Overview
No drug interactions have been established.
9.3. Drug-Behaviour Interactions
The interaction of ANDEMBRY with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4. Drug-Drug Interactions
No dedicated drug interaction studies have been conducted in humans. Garadacimab has only been studied as a monotherapy and not in combination with other products indicated for long-term prophylaxis of HAE.
There is very limited clinical data on the use of concomitant antiplatelet/anticoagulant medication with garadacimab. Garadacimab inhibits the activity of activated FXII. FXII activation initiates the intrinsic pathway of the coagulation cascade. The impact on the concomitant use of anticoagulants which inhibit the extrinsic pathway is unknown.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Coagulation Tests
Garadacimab can prolong activated partial thromboplastin time (aPTT) due to an interaction of garadacimab with the aPTT assay. The reagents used in the aPTT laboratory test initiate intrinsic coagulation through the activation of FXII in the contact system, therefore inhibition of plasma FXIIa by garadacimab can prolong aPTT in this assay. None of the increases in aPTT in patients treated with garadacimab were associated with bleeding adverse events. There were no clinically relevant differences in international normalized ratio (INR) between treatment groups.
Interference with D-Dimer test
Reductions in mean D-dimer values were observed in patients treated with garadacimab, including some patients with values below the lower limit of normal. The clinical relevance of this observation is unclear.
10. Clinical Pharmacology
10.1. Mechanism of Action
Garadacimab is a fully human IgG4/lambda recombinant monoclonal antibody which binds to the catalytic domain of activated Factor XII (FXIIa and βFXIIa) and potently inhibits its catalytic activity. FXII is the first factor activated in the contact activation pathway and initiates the inflammatory bradykinin-producing kallikrein-kinin system. The inhibition of FXIIa prevents the activation of prekallikrein to kallikrein and the generation of bradykinin, which is associated with inflammation and swelling in HAE attacks, thus potentially reducing the cascade of events leading to an HAE attack.
10.2. Pharmacodynamics
Concentration-dependent inhibition of FXIIa-mediated kallikrein activity was demonstrated after subcutaneous administration of ANDEMBRY in patients with HAE.
10.3. Pharmacokinetics
Table 3 provides Garadacimab pharmacokinetics and steady-state exposure, based on population pharmacokinetic (PK) analysis, in HAE patients given 400 mg (2 x 200 mg) subcutaneous loading dose followed by 200 mg once monthly subcutaneously in Trial 1. Following subcutaneous administration of ANDEMBRY, peak plasma concentration is reached within ~6 days, and terminal elimination half-life is ~19 days. Steady state garadacimab exposure was achieved after the initial subcutaneous administration of loading dose of 400 mg (2 x 200 mg).
Table 3 – Mean (SD) Pharmacokinetic Parameters of Garadacimab Following SubcutaneousAdministration (Trial 1)
| Pharmacokinetic Parameters | Garadacimab 200 mg once monthly (N=39) |
|---|---|
| CL/F (L/h) | 0.0217 (0.00793) |
| Vc/F (L) | 7.42 (4.20) |
| AUCtau,ss (mcg∙h/mL) | 10300 (3380) |
| Cmax,ss (mcg/mL) | 21.2 (6.58) |
| Cmin,ss (mcg/mL) | 9.30 (3.73) |
| tmax (h) | 137 (91.0, 175)* |
| t1/2 (h) | 445 (97.4) |
CL/F: apparent clearance; Vc/F: apparent volume of distribution; AUCtau,ss area under the curve over the dosing interval at steady-state; Cmax,ss: maximum concentration at steady-state; Cmin,ss: minimum concentration at steady-state; tmax: time to maximum concentration; t1/2: terminal elimination half-life.
*Median (range) presented for tmax
Absorption
Following subcutaneous administration, the time to maximum concentration is approximately 6 days. The site of subcutaneous injection (thigh, arm, or abdomen) did not affect the absorption of garadacimab. The absorption rate of garadacimab was 0.00824/h. The mean absolute bioavailability of garadacimab in HAE patients was 39.5% on the basis of the population pharmacokinetic analysis.
Distribution
The mean (SD) apparent volume of distribution of garadacimab in patients with HAE was 7.42 litres (4.20). Garadacimab is a monoclonal antibody and is not expected to bind to plasma proteins.
Metabolism
Similar to other monoclonal antibodies, garadacimab is expected to be degraded by enzymatic proteolysis into small peptides and amino acids. Therefore, specific metabolism studies were not conducted with garadacimab.
Elimination
Garadacimab has a mean (SD) apparent clearance of 0.0217 L/h (0.00793) and a terminal elimination half-life of approximately 19 days.
Special Populations and Conditions
Population pharmacokinetic analyses showed that age, gender, and race did not meaningfully influence the pharmacokinetics of garadacimab after correcting for body weight. Body weight was identified as an important covariate describing the variability of clearance and volume of distribution, resulting in higher exposure in lighter patients. However, this difference is not clinically relevant and no dose adjustments are recommended for any of these demographics.
Pediatrics
Based on population pharmacokinetic analyses that included pediatric patients (12 to 17 years, N=11), age does not have a clinically meaningful impact on the PK of garadacimab and no dose adjustments are recommended.
Pharmacokinetics of garadacimab in pediatric patients below the age of 12 has not been investigated.
Geriatrics
Based on population pharmacokinetic analyses that included elderly patients (≥65 years, N=13), age does not have a clinically meaningful impact on the PK of garadacimab and no dose adjustments are recommended.
Hepatic Insufficiency
No dedicated studies have been conducted to evaluate the PK of garadacimab in hepatic impairment patients. Based on population pharmacokinetic analysis, hepatic impairment had no effect on the PK of garadacimab.
Renal Insufficiency
No dedicated studies have been conducted to evaluate the PK of garadacimab in renal impairment patients. Based on population pharmacokinetic analysis, renal impairment (estimated GFR: ≥90 mL/min/1.73m2 [normal, N=145], 60 to <90 mL/min/1.73m2 [mild, N=26], and 30 to <60 mL/min/1.73m2 [moderate, N=2]) had no effect on the PK of garadacimab.
Concomitant medications
Based on population PK analyses, the use of analgesic, antibacterial, antihistamine, anti-inflammatory and anti-rheumatic medications had no effect on the PK of garadacimab.
Based on population PK analyses, for breakthrough HAE attacks, use of rescue medications such as plasma-derived and recombinant C1-INH or icatibant had no effect on the PK of garadacimab.
10.4. Immunogenicity
All therapeutic proteins have the potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
In Trial 1, treatment with garadacimab has been associated with development of low-titre treatment emergent anti-drug antibodies (ADA) in 1 (2.6%) of treated subjects during the 6-month period. In Trial 2, 5 (2.9%) treated subjects including 1 subject rolled over from Trial 1 developed low-titre treatment emergent ADAs.
The development of ADA against garadacimab did not affect pharmacokinetics (PK), pharmacodynamics (PD), safety or clinical response.
A standalone neutralizing antibody assay has not been developed. The potential impact of neutralizing antibodies on garadacimab exposure, efficacy, pharmacodynamics, and safety has not been assessed.
- 11. Storage, Stability, and Disposal
- • Store in a refrigerator (+2⁰C to +8⁰C). Do not freeze.
- • Keep the solution (prefilled syringe with needle safety device or prefilled pen) in the outer carton in order to protect from light.
- • The solution (prefilled syringe with needle safety device or prefilled pen) may be stored at room temperature up to +25°C for up to 2 months, but not beyond the expiry date. Do not return ANDEMBRY to refrigerated storage after storage at room temperature up to +25 °C.
- • Discard any unused product after each infusion in accordance with local requirements.
12. Special Handling Instructions
The ANDEMBRY prefilled syringe/prefilled pen is for single-use only. There are no special handling instructions.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: garadacimab
Chemical name: IgG4/lambda or IgG4/λ-light chain
Molecular formula and molecular mass: Garadacimab has a molecular weight of approximately 148 kDa.
Physicochemical properties: slightly opalescent to clear, brownish-yellow to yellow liquid.
Pharmaceutical standard: FXIIa inhibitor monoclonal antibody
Product Characteristics:
Garadacimab is a recombinant, fully human, monoclonal antibody (IgG4/λ-light chain) produced by recombinant DNA technology in Chinese Hamster Ovarian (CHO) cells.
14. Clinical Trials
14.1. Clinical Trials by Indication
Hereditary Angioedema (HAE)
Table 4 – Summary of patient demographics for clinical trials in HAE Attacks
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex (%) |
| Phase 3-Trial 1 (NCT046 56418) | multicenter, randomized, double-blind, placebo-controlled parallel group study | garadacimab 200 mg SC Q4W after an initial 400 mg SC loading dose or placebo for a 6-month treatment period | 39 (garadacimab 200 mg) 25 (placebo) | 41.2 years (12-69) | M (40.6%) / F (59.4%) |
| Phase 3-Trial 2 (NCT047 39059) | multicenter, open-label extension study | garadacimab 200 mg monthly after an initial 400 mg loading dose. Planned Study duration: 4.6 years | 161 (garadacimab 200 mg) | 42.3 years (13-73) | M (37.3%) / F (62.7%) |
M = male; F = female; SC = subcutaneous
Trial 1 (NCT04656418):
The efficacy of ANDEMBRY for the prevention of hereditary angioedema attacks in patients 12 years of age and older with Type I or II HAE was demonstrated in a phase 3, multicenter, randomized, double-blind, placebo-controlled parallel group study.
The study included 64 adult and pediatric patients (12 years of age and older) who experienced at least 2 attacks during the up to 2-month run-in period. Patients were randomized into 2 parallel treatment arms in a 3:2 ratio (garadacimab 200 mg monthly after an initial 400 mg loading dose or volume-match placebo) for a 6-month treatment period. Patients were required to discontinue other prophylactic HAE medications prior to entering the study. All patients were allowed to use on-demand medications for treatment of HAE attacks during the study.
Overall, 87.5% of patients had Type I HAE. A family history of HAE was reported for 89.1%, a history of laryngeal edema attacks for 59.4% of patients and 32.8% were on prior prophylaxis. During the study run-in period, attack rates of ≥3 attacks/month were observed in 59.4% of patients overall.
The primary endpoint was the difference in time-normalized number of investigator-confirmed attacks of HAE (Day 1 to 182) between ANDEMBRY and placebo. The key secondary endpoints were the percent reduction in the time-normalized number of HAE attacks (Day 1 to 182); the number of attack-free subjects through Day 91; and the percentage of subjects rating therapy as “good” or better (ie, “excellent”) through the SGART at Day 182.
The results for the primary and key secondary endpoints in the Intent-to-Treat (ITT) population are presented below in Table 5.
Table 5 – Results of Primary and Key Secondary Efficacy Endpoints at 6 months in Subjects with HAE in Trial 1 (NCT04656418)
| ANDEMBRY 200 mg N = 39 | Placebo N = 24a | ||||||||||
| Primary Endpoint | |||||||||||
| Time-normalized Number of HAE Attacks Per Month | |||||||||||
| Number of HAE Attacks during Treatment Period | 63 | 264 | |||||||||
| Adjusted LS meanb (95% CI) | 0.22 (0.11, 0.47) | 2.07 (1.49, 2.87) | |||||||||
| HAE attacks ratiob (95% CI) | 0.11 (0.05, 0.24) | ||||||||||
| p-value* | < 0.001 | ||||||||||
ANDEMBRY 200 mg N = 39 | Placebo N = 24a | ||||||||||
| Secondary Endpoints | |||||||||||
| Patients who were attack free from day 1 through the end of month 3 | |||||||||||
| Percentage of patients | 71.8% | 8.3% | |||||||||
| p-value* | < 0.001 | ||||||||||
| Good or Excellent Responses to the Subject’s Global Assessment of Response to Therapy (SGART) | |||||||||||
| Percentage of patients | 81.6% | 33.3% | |||||||||
| p-value* | < 0.001 | ||||||||||
CI = confidence interval; HAE = hereditary angioedema; ITT = intention-to-treat; LS = least squares; N = number of patients in the ITT Analysis Set; SD = standard deviation
a Twenty-five (N=25) subjects were originally randomized into the placebo arm; however, one patient had a Treatment Period of less than 30 Days and was therefore not included in the efficacy analyses.
b Generalized linear model for count data (Poisson regression model) adjusted for baseline attack rate.
* A hierarchical testing procedure controls for the overall alpha level of 5%.
Additional non-hierarchically tested secondary endpoints from day 1 to 182 were the mean (median) time-normalised number of HAE attacks requiring on-demand treatment, 0.23 (0.0) in subjects treated with ANDEMBRY compared to 1.86 (1.35) in the placebo group, and the mean (median) time-normalised number of moderate to severe HAE attacks, 0.13 (0.0) in subjects treated with ANDEMBRY compared to 1.35 (0.83) in the placebo group. The proportion of patients who remained attack free from the first dose to the end of trial (day 1 to 182) was 62% compared to 0% in the placebo group.
The proportion of subjects who achieved an improvement in quality of life as evaluated by the Angioedema Quality of Life (AE-QoL) questionnaire (minimal clinically important difference ≥6 for the AE-QoL total score), which measures functioning, fatigue/mood, fear/shame, and nutrition, was 87.9% for the ANDEMBRY® and 55.0% for the placebo.
While very limited, the efficacy profile in pediatric patients with HAE 12 years of age and older (n=6) appeared similar to that of the adult population.
Trial 2 (NCT04739059).
Trial 2 is a phase 3, multicenter, open-label extension study designed to investigate long-term safety and efficacy of ANDEMBRY that enrolled a total of 161 patients. The 161 patients are from: Trial 1 (n=57), a phase 3, multicenter, randomized, double-blind, placebo-controlled parallel group study; a phase 2 (n=35), multicenter, randomized, placebo-controlled, parallel-arm study; and the remaining patients (n=69) are newly enrolled and naïve to treatment with ANDEMBRY.
At the time of the interim analysis 2 (data cut of 13-FEB-2023), for the 36 garadacimab-treated patients from Trial 1 who rolled over into the open-label extension study, the median duration of exposure was 11.6 months (range: 4.9 to 16.3 months) and the associated mean (SD) time-normalized number of HAE attacks per month was 0.11 (0.316) attacks/month.
16. Non-Clinical Toxicology
General Toxicology: Garadacimab was administered at doses of 0 (vehicle), 3, 10, 30, or 100 mg/kg by intravenous (IV) bolus injection twice per week, or 0 (vehicle), 60, or 200 mg/kg by subcutaneous (SC) injection twice per week, in mice for up to 4 weeks and in cynomolgus monkeys for up to 26 weeks. Animals showed increased activated partial thromboplastin times. Some mice and monkeys developed clinical signs of anaphylaxis and were euthanized. One monkey developed skeletal muscle lesions related to the immune response to a heterologous protein. A NOAEL was not determined in mice. The NOAELs in monkeys were 30 mg/kg/occasion by IV and 60 mg/kg/occasion by SC administration (equal to 31.5 and 37-fold the recommended human dose of 200 mg SC once monthly based on area under the curve [AUC]) due to anaphylaxis observed at higher doses.
Genotoxicity: Animal studies have not been conducted to evaluate the genotoxic potential of garadacimab.
Carcinogenicity: Animal studies have not been conducted to evaluate the carcinogenic potential of garadacimab.
Reproductive and Developmental Toxicology: Garadacimab was administered to male rabbits at doses of 0 (vehicle), 10, 30, or 100 mg/kg intravenously once every three days beginning 27 days before cohabitation, during cohabitation and continuing until 8 days post-cohabitation. In a separate study, female rabbits were administered garadacimab at the same doses beginning 12 days before cohabitation and continuing until gestational day (GD) 7. Male and female fertility were unaffected based upon a lack of adverse findings on mating, fecundity, fertility indices, maternal reproductive parameters, embryo survival or sperm assessment in sexually mature rabbits that received garadacimab up to doses of 100 mg/kg (resulting in approximately 83- and 103-fold the exposure in females and males, respectively, at the recommended human dose of 200 mg SC once monthly based on AUC).
In the embryofetal development study, pregnant rabbits were administered garadacimab at doses of 0 (vehicle), 10, 30, or 100 mg/kg intravenously once every 3 days from GD 6 to 18. No effects on embryofetal development were reported at doses up to 100 mg/kg (resulting in approximately 104-fold the exposure at the recommended human dose of 200 mg SC once monthly based on AUC).
In a pre- and post-natal development study, pregnant rabbits were administered garadacimab at doses of 0 (vehicle), 10, 30, or 100 mg/kg subcutaneously, or 100 mg/kg intravenously, once every 5 days, from GD 7 until weaning on lactation day 38. Maternal garadacimab treatment had no effect on embryo-fetal development, postnatal development, survival, growth, neurobehavioral, and reproductive performances of offspring through 6 months of age. The maternal and developmental NOAELs were 100 mg/kg by SC or IV injection (53- and 76-fold the exposure at the recommended human dose of 200 mg SC once monthly based on AUC, respectively).
Garadacimab crossed the placenta in rabbits. At GD 29, fetal plasma garadacimab concentrations were 40.8 to 136.6% of maternal concentrations after subcutaneous administration of 10 to 100 mg/kg and were equal to maternal concentrations after intravenous administration of 100 mg/kg.
Juvenile Toxicity: No dedicated juvenile toxicity studies have been performed for garadacimab.