


Product Monograph - Apo-Cefuroxime
Recent Major Label Changes
| 2026-06 |
|---|---|
| 2026-06 |
| 2026-06 |
| 2026-06 |
| 2026-06 |
| 2026-06 |
| 2026-06 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
- 1.
Indications ................................................................................................................... 5
1.1. Pediatrics .................................................................................................................. 5
1.2. Geriatrics .................................................................................................................. 5
- 2. Contraindications ......................................................................................................... 6
- 3. Serious Warnings and Precautions Box ........................................................................ 6
- 4.
Dosage and Administration .......................................................................................... 6
4.1. Dosing Considerations .............................................................................................. 6
4.2. Recommended Dose and Dosage Adjustment ......................................................... 6
4.4. Administration ......................................................................................................... 7
4.5. Missed Dose ............................................................................................................. 7
- 5. Overdose...................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................ 8
- 7.
Warnings and Precautions ............................................................................................ 8
Cardiovascular ................................................................................................................... 8
Driving and Operating Machinery ..................................................................................... 8
Gastrointestinal ................................................................................................................. 9
Hematologic ...................................................................................................................... 9
Immune ........................................................................................................................... 10
Monitoring and Laboratory Tests .................................................................................... 10
Neurologic ....................................................................................................................... 10
Renal .............................................................................................................................. 11
Sensitivity/Resistance ...................................................................................................... 11
Skin .............................................................................................................................. 11
7.1. Special Populations................................................................................................ 11
7.1.1. Pregnancy ................................................................................................... 11
7.1.2. Breastfeeding .............................................................................................. 12
7.1.3. Pediatrics .................................................................................................... 12
7.1.4. Geriatrics .................................................................................................... 12
- 8.
Adverse Reactions ...................................................................................................... 12
8.2. Clinical Trial Adverse Reactions .............................................................................. 12
8.5. Post-Market Adverse Reactions ............................................................................. 13
- 9.
Drug Interactions ....................................................................................................... 14
9.3. Drug-Behaviour Interactions .................................................................................. 14
9.4. Drug-Drug Interactions ........................................................................................... 14
9.5. Drug-Food Interactions .......................................................................................... 15
9.6. Drug-Herb Interactions .......................................................................................... 15
9.7. Drug-Laboratory Test Interactions ......................................................................... 15
- 10.
Clinical Pharmacology ................................................................................................ 15
10.1. Mechanism of Action ............................................................................................. 15
10.2. Pharmacodynamics ................................................................................................ 15
10.3. Pharmacokinetics ................................................................................................... 16
- 11. Storage, Stability, and Disposal .................................................................................. 18
Part 2: Scientific Information ................................................................................................. 19
- 13. Pharmaceutical Information ....................................................................................... 19
- 14.
Clinical Trials .............................................................................................................. 19
14.2. Comparative Bioavailability Studies ....................................................................... 19
- 15. Microbiology .............................................................................................................. 20
- 16. Non-Clinical Toxicology .............................................................................................. 23
- 17. Supporting Product Monographs ............................................................................... 29
Patient Medication Information ............................................................................................ 30
Part 1: Healthcare Professional Information
1. Indications
APO-CEFUROXIME (cefuroxime axetil tablets) is indicated for the treatment of patients with mild to moderately severe infections caused by susceptible strains of the designated organisms in the following diseases:
- Upper Respiratory Tract Infections:
Pharyngitis and tonsillitis caused by Streptococcus pyogenes.
Otitis Media caused by Streptococcus pneumoniae, Streptococcus pyogenes (group A beta-hemolytic streptococci), Haemophilus influenzae (beta-lactamase negative and beta-lactamase positive strains) or Moraxella catarrhalis.
- Skin Structure Infections:
Skin structure infections caused by Staphylococcus aureus (methicillin susceptible), Streptococcus pyogenes or Streptococcus agalactiae.
Susceptibility to cefuroxime axetil will vary with geography and time. Cefuroxime axetil should be used in accordance with local official antibiotic prescribing guidelines and local susceptibility data (see 15. Microbiology). Bacteriologic studies to determine the causative organism and its susceptibility to cefuroxime should be performed. Once these results become available antibiotic treatment should be adjusted if required.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of APO-CEFUROXIME and other antibacterial drugs, APO-CEFUROXIME should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1. Pediatrics
Pediatrics (< 12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of APO-CEFUROXIME in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 4.2. Recommended Dose and Dosage Adjustment and 7.1.3 Pediatrics.
1.2. Geriatrics
Geriatrics: No data are available to Health Canada regarding APO-CEFUROXIME; therefore, Health Canada has not authorized an indication for geriatric use.
2. Contraindications
APO-CEFUROXIME is contraindicated for patients who have shown Type 1 hypersensitivity to cefuroxime, to any of its components, or to any of the cephalosporin group of antibiotics. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
- Hemolytic Anemia: APO-CEFUROXIME should not be used in patients with a history of cephalosporin-associated hemolytic anemia since the recurrence of hemolysis is much more severe. See 7. Warnings and Precautions, Hemolytic anemia, 7. Warnings and Precautions, Monitoring and Laboratory Tests and 8.2. Clinical Trial Adverse Reactions, Blood and lymphatic system disorders.
- Hypersensitivity: Serious and occasionally fatal hypersensitivity (anaphylactic) and severe cutaneous adverse reactions (SCAR) have been reported in patients receiving therapy with beta-lactams, including cefuroxime. See 2. Contraindications, 7. Warnings and Precautions, Hypersensitivity reactions, and 7. Warnings and Precautions, Severe cutaneous adverse reactions.
4. Dosage and Administration
4.1. Dosing Considerations
The dose of cefuroxime that is selected to treat an individual infection should take into account:
- The expected pathogens and their likely susceptibility to cefuroxime axetil
- The site of the infection
- The age, weight and renal function of the patient; as shown below.
The duration of therapy should be determined by the type of infection and the response of the patient, and should generally not be longer than recommended.
4.2. Recommended Dose and Dosage Adjustment
The usual duration of treatment for APO-CEFUROXIME tablets is 7 to 10 days.
For β-hemolytic streptococcal infections, therapy should be continued for at least 10 days.
Adults and Children 12 Years of Age and Older:
The usual recommended dosage is 250 mg twice a day. However, dosage may be modified according to the type of infection present as indicated below:
| Type of Infection | Dosage |
| pharyngitis, tonsillitis, sinusitis, bronchitis, skin structure infections | 250 mg twice daily |
| more severe infections e.g. pneumonia | 500 mg twice daily |
Infants and Children less than 12 Years of Age
APO-CEFUROXIME tablets are not recommended for infants and children less than 12 years of age.
Renal Insufficiency
APO-CEFUROXIME is primarily excreted by the kidneys. In patients with markedly impaired renal function, it is recommended that the dosage of APO-CEFUROXIME be reduced to compensate for its slower excretion (see the table below).
| Creatinine Clearance | T1/2 (hours) | Recommended Dosage |
| ≥30 mL/min/1.73m2 | 1.4 - 2.4 | No dose adjustment necessary (standard dose of 125 mg to 500 mg given twice daily) |
| 10 - 29 mL/min/1.73m2 | 4.6 | Standard individual dose given every 24 hours |
| <10 mL/min/1.73m2 | 16.8 | Standard individual dose given every 48 hours |
| During haemodialysis | 2 - 4 | A single additional standard individual dose should be given at the end of each dialysis |
The safety and efficacy of the proposed dosing adjustment has not been established.
4.4. Administration
For optimal absorption, APO-CEFUROXIME should be taken with food.
4.5. Missed Dose
If the patient misses a dose, inform the patient to take the missed dose as soon as possible, then continue with the normal dose schedule. The patient should not take two doses at once to make up for a missed dose.
5. Overdose
Overdose can lead to neurological sequelae including encephalopathy, convulsions and coma.
Symptoms of overdose can occur if the dose is not reduced appropriately in patients with renal impairment (see 4.2. Recommended Dose and Dosage Adjustment).
Other than general supportive treatment, no specific antidote is known. Excessive serum levels of cefuroxime can be reduced by dialysis. For treatment of hypersensitive reactions, see 7. Warnings and Precautions, Immune.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1: Dosage Forms, Strengths, and Composition
Description
250 mg tablets: each white to creamish white capsule-shaped, biconvex, film-coated tablet, one side engraved "APO", the other side engraved "C250", contains cefuroxime axetil equivalent to 250 mg of cefuroxime base. Available in bottles of 60 and 100.
500 mg tablets: each white to creamish white, capsule-shaped, biconvex, film-coated tablet, one side engraved "APO", the other side engraved "C500", contains cefuroxime axetil equivalent to 500 mg of cefuroxime base. Available in bottles of 60 and 100.
7. Warnings and Precautions
See 3. Serious Warnings and Precautions Box.
Cardiovascular
Kounis syndrome (See Immune and 8.5. Post-Market Adverse Reactions).
Driving and Operating Machinery
As this medicine may cause dizziness, patients should be warned to be cautious when driving or operating machinery.
| Route of Administration | Dosage Form/ Strength/ Composition | Non-Medicinal Ingredients |
| Oral | Tablet / 250 mg, 500 mg of cefuroxime axetil | Colloidal silicon dioxide, crospovidone, hydroxypropyl cellulose, hydroxypropyl methylcellulose, magnesium stearate, polyethylene glycol, and titanium dioxide |
Gastrointestinal
Broad-spectrum antibiotics including APO-CEFUROXIME should be administered with caution to individuals with a history of gastrointestinal disease, particularly colitis.
Clostridium difficile-Associated Disease
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents including APO-CEFUROXIME (see 8.5. Post-Market Adverse Reactions, Gastrointestinal disorders). CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases.
Hematologic
Hemolytic anemia
APO-CEFUROXIME should not be used in patients with a history of cephalosporin-associated hemolytic anemia since the recurrence of hemolysis is much more severe (see 3. Serious Warnings and Precautions Box and 8.2. Clinical Trial Adverse Reactions, Blood and lymphatic system disorders).
An immune mediated hemolytic anemia has been observed in patients receiving cephalosphorin class antibacterials, including APO-CEFUROXIME. Severe cases of hemolytic anemia, including fatalities, have been reported in both adults and children. If a patient develops anemia anytime during, or within 2 to 3 weeks subsequent to the administration of APO-CEFUROXIME, the diagnosis of a cephalosphorin-associated anemia should be considered and the drug discontinued until the etiology is determined.
Patients may benefit from periodic monitoring for signs and symptoms of hemolytic anemia, including measurement of hematological parameters or drug-induced antibody testing, where appropriate (see Monitoring and Laboratory Tests).
Immune
Hypersensitivity reactions
Before therapy with APO-CEFUROXIME (cefuroxime axetil) is instituted, careful inquiry should be made to determine whether the patient has had previous hypersensitivity reactions to cefuroxime, cephalosporins, penicillin, or other drugs. APO-CEFUROXIME should be administered with caution to any patient who has demonstrated some form of allergy, particularly to drugs. There is some clinical and laboratory evidence of partial cross-allergenicity of the cephalosporins and penicillin. Special care is indicated in patients who have experienced allergic reaction to penicillins or other beta-lactam antibiotics because there is a risk of cross-sensitivity. As with all beta-lactam antibacterial agents, serious and occasionally fatal hypersensitivity reactions have been reported (see 2. Contraindications, 3. Serious Warnings and Precautions Box, 8.2. Clinical Trial Adverse Reactions, Immune system disorders, and 8.5. Post-Market Adverse Reactions, Immune system disorders). If an allergic reaction to APO-CEFUROXIME occurs, treatment should be discontinued and standard agents (e.g. epinephrine, antihistamines, corticosteroids) administered as necessary.
There have been reports of hypersensitivity reactions which progressed to Kounis syndrome (acute allergic coronary arteriospasm that can result in myocardial infarction, see 8.5. Post-Market Adverse Reactions). In case of severe hypersensitivity reactions, treatment with APO-CEFUROXIME must be discontinued immediately and adequate emergency measures must be initiated.
Jarisch-Herxheimer reaction
The Jarisch-Herxheimer reaction has been seen following cefuroxime axetil treatment of Lyme disease. It results directly from the bactericidal activity of cefuroxime axetil on the causative bacteria of Lyme disease, the spirochaete Borrelia burgdorferi (see 8.5. Post-Market Adverse Reactions).
Monitoring and Laboratory Tests
Patients may benefit from periodic monitoring for signs and symptoms of hemolytic anemia, including measurement of hematological parameters or drug-induced antibody testing, where appropriate (see 3. Serious Warnings and Precautions Box, 7. Warnings and Precautions, Hematologic, and 8.2. Clinical Trial Adverse Reactions, Blood and lymphatic system disorders).
Neurologic
Cephalosporins have been associated with the occurrence of seizures. A known risk factor is renal impairment without dosage adjustment; however, seizures have also been described in individuals without a preceding history of renal impairment whose renal function deteriorates while taking the cephalosporin.
If seizures associated with APO-CEFUROXIME occur, APO-CEFUROXIME should be discontinued if clinically appropriate. Anticonvulsant therapy can be given if clinically indicated. See 8.5. Post-Market Adverse Reactions.
Renal
Cefuroxime is substantially excreted by the kidney, and the risk of adverse reactions may be greater in patients with impaired renal function. It may be useful to monitor renal function in patients with renal impairment. See 4.2. Recommended Dose and Dosage Adjustment, Renal Insufficiency and 10.3. Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency.
Sensitivity/Resistance
Development of drug-resistant bacteria
Prescribing APO-CEFUROXIME in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Overgrowth of non-susceptible organisms
As with other antibiotics, use of APO-CEFUROXIME may result in the overgrowth of Candida. Prolonged use may also result in the overgrowth of other non-susceptible organisms (e.g. enterococci and Clostridium difficile), which may require interruption of treatment. Repeated evaluation of the patient's condition is essential. If superinfection occurs during therapy, appropriate measures should be taken. Should an organism become resistant during antibiotic therapy, APO-CEFUROXIME should be discontinued and another appropriate antibiotic should be substituted.
Skin
Severe cutaneous adverse reactions
Severe cutaneous adverse reactions (SCAR) such as acute generalized exanthematous pustulosis (AGEP), drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN) have been reported in association with beta-lactam treatment. When SCAR is suspected, APO-CEFUROXIME should be discontinued and appropriate therapy and/or measures should be taken. See 3. Serious Warnings and Precautions Box and 8.5. Post-Market Adverse Reactions, Skin and Subcutaneous Tissue Disorders.
7.1. Special Populations
7.1.1. Pregnancy
The safety of APO-CEFUROXIME in pregnancy has not been established. The use of APO-CEFUROXIME in pregnant women requires that the likely benefit from the drug be weighed against the possible risk to the mother and fetus. Animal studies following parenteral administration have shown cefuroxime to affect bone calcification in the fetus and to cause maternal toxicity in the rabbit. Reproduction studies that have been performed in mice and rats at oral doses of up to 50 to 160 times the human dose have revealed no evidence of impaired fertility or harm to the fetus due to cefuroxime axetil. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
7.1.2. Breastfeeding
Cefuroxime is excreted in human milk in small quantities. Consideration should be given to discontinuing breastfeeding temporarily during treatment with APO-CEFUROXIME. APO-CEFUROXIME should only be used during breastfeeding if the potential benefit justifies the potential risk to the breastfed child. A risk of diarrhea and fungus infection of the mucous membranes in breastfed infants cannot be excluded.
7.1.3. Pediatrics
The safety of the use of APO-CEFUROXIME in infants under the age of 3 months has not been established (See 4.2. Recommended Dose and Dosage Adjustment).
7.1.4. Geriatrics
The elimination of APO-CEFUROXIME may be decreased due to impairment of renal function. Health Canada has not authorized an indication for geriatric use (see 1.2. Geriatrics).
8. Adverse Reactions
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect the frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
The following adverse reactions have been reported:
Blood and lymphatic system disorders: Eosinophilia, and very rarely hemolytic anemia (see 7. Warnings and Precautions, Hematologic).
Gastrointestinal disorders (approximately 8% of patients): Diarrhea (5.6%), nausea (2.4%), vomiting (2.0%), loose stools (1.3%). Reports of abdominal pain have occurred.
General disorders and administration site conditions: As with other cephalosporins, there have been rare reports of drug fever.
Immune system disorders (1.3% of patients): Hypersensitivity reactions to APO-CEFUROXIME may occur in patients who report delayed hypersensitivity to penicillins (see 7. Warnings and Precautions, Immune).
Investigations: Increased erythrocyte sedimentation rate, decreased hemoglobin, positive Coomb’s test. Transient increases of hepatic enzyme levels [ALT, AST, LDH] (3% of patients).
The following adverse reactions have been observed to occur, although infrequently, in association with parenteral cefuroxime sodium and may be potential adverse effects of oral cefuroxime axetil: Transient increases in serum bilirubin, creatinine, alkaline phosphatase, and urea nitrogen (BUN).
Nervous system disorders (2.2% of patients): Headache and dizziness.
The following adverse reactions have been observed to occur, although infrequently, in association with parenteral cefuroxime sodium and may be potential adverse effects of oral cefuroxime axetil: drowsiness.
Reproductive system and breast disorders: The following adverse reactions have been observed to occur, although infrequently, in association with parenteral cefuroxime sodium and may be potential adverse effects of oral cefuroxime axetil: vaginitis.
Respiratory system and mediastinal disorders: Shortness of breath and rare reports of bronchospasm.
Skin and subcutaneous tissue disorders: Rashes (0.6%), pruritus (0.3%), urticaria (0.2%). In addition, the incidence of diaper rash (1.4%) has been associated with cefuroxime axetil in children.
8.5. Post-Market Adverse Reactions
In addition to adverse events reported during clinical trials, the following events have been identified during clinical practice in patients treated with cefuroxime axetil and were reported spontaneously. Data are generally insufficient to allow an estimate of incidence or to establish causation.
Blood and lymphatic system disorders: Thrombocytopenia, and leucopenia (sometimes profound).
Cardiac Disorders: Kounis syndrome.
Gastrointestinal disorders: Pseudomembranous colitis (see 7. Warnings and Precautions, Gastrointestinal, Clostridium difficile-Associated Disease).
Hepatobiliary disorders: Jaundice (predominantly cholestatic) and hepatitis have been reported very rarely.
Immune System Disorders: The following hypersensitivity reactions have been reported: anaphylaxis, angioedema, Jarisch-Herxheimer reaction, pruritus, rash, serum sickness-like reaction, urticaria.
Infections and Infestations: Candida overgrowth.
Nervous system disorders: Seizure. See 7. Warnings and Precautions, Neurologic.
Renal and urinary disorders: Renal dysfunction.
Skin and Subcutaneous Tissue Disorders: Erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis.
9. Drug Interactions
9.3. Drug-Behaviour Interactions
The interaction of APO-CEFUROXIME with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Drug product(s) | Source of evidence | Effect |
| Aminoglycosides | T | The concomitant administration of aminoglycosides and some cephalosporins has caused nephrotoxicity. There is no evidence that APO-CEFUROXIME, when administered alone, is nephrotoxic, although transient elevations of BUN and serum creatinine have been observed in clinical studies. However, the effect of administering APO-CEFUROXIME concomitantly with aminoglycosides is not known. |
| Diuretics | CT | Studies suggest that the concomitant use of potent diuretics, such as furosemide and ethacrynic acid, may increase the risk of renal toxicity with cephalosporins. |
| Drugs which reduce gastric acidity | T | Drugs which reduce gastric acidity may result in a lower bioavailability of APO-CEFUROXIME compared with that of the fasting state and tend to cancel the effect of enhanced post-prandial absorption. |
| Oral contraceptives | T | In common with other antibiotics, cefuroxime axetil may affect the gut flora, leading to lower estrogen reabsorption and reduced efficacy of combined oral contraceptives. |
Legend: CT = Clinical Trial; T = Theoretical
9.5. Drug-Food Interactions
For optimal absorption, APO-CEFUROXIME should be taken with food (see 4.4. Administration).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
A false-positive reaction for glucose in the urine may occur with copper reduction tests (Benedict's or Fehling's solution or with Clinitest Tablets) but not with enzyme-based tests for glycosuria (e.g. Clinistix, Tes-Tape). As a false-negative result may occur in the ferricyanide test, it is recommended that either the glucose oxidase or hexokinase method be used to determine blood plasma glucose levels in patients receiving APO-CEFUROXIME.
Cefuroxime does not interfere with the assay of serum and urine creatinine by the alkaline picrate method.
Cephalosporins as a class tend to be absorbed onto the surface of red cell membranes and react with antibodies directed against the drug to produce a positive Coombs' test (which can interfere with cross-matching of blood) and very rarely hemolytic anemia (see 7. Warnings and Precautions, Monitoring and Laboratory Tests and 8.2. Clinical Trial Adverse Reactions).
10. Clinical Pharmacology
10.1. Mechanism of Action
Cefuroxime axetil is an orally active prodrug of cefuroxime. After oral administration, cefuroxime axetil, as cefuroxime axetil tablets, is absorbed from the gastrointestinal tract and rapidly hydrolyzed by nonspecific esterases in the intestinal mucosa and blood to release cefuroxime into the blood stream. Conversion to cefuroxime, the microbiologically active form, occurs rapidly. The inherent properties of cefuroxime are unaltered after its administration as cefuroxime axetil. Cefuroxime exerts its bactericidal effect by binding to an enzyme or enzymes referred to as penicillin-binding proteins (PBPs) involved in bacterial cell wall synthesis. This binding results in inhibition of bacterial cell wall synthesis and subsequent cell death. Specifically, cefuroxime shows high affinity for PBP 3, a primary target for cefuroxime in gram-negative organisms such as E. coli.
10.2. Pharmacodynamics
Animal Pharmacology
The secondary pharmacological effects of cefuroxime axetil have been investigated in mice, rats, and dogs following a single oral dose. Negative controls were administered a placebo suspension while positive controls received mecamylamine HCI (an inhibitor of gastrointestinal propulsion). The results are summarized in Table 3.
Table 3: Secondary pharmacological actions in animals after a single oral dose of cefuroxime axetil
| Animal | Dose (mg/kg) | No. of Animals* | Pharmacological Actions | Observation Times | Effects |
| mice | 0.5 | 10 | pupil diameter, body temperature, gross behaviour | 0 - 1h, 24h intervals for 7d | decreased body temperature in females |
| rat | 0.5 | 10 | pupil diameter, body temperature, gross behaviour | 0 - 1h, 24h intervals for 7d | decreased body temperature in females |
| dog | 0.5 | 2 | BP, HR, ECG, gross behaviour | 2.25, 3, 6, 24h | none |
| rat | 0.5 | 10 | gastrointestinal propulsion | 0.75h | none |
* Each group consisted of equal numbers of males and females
As can be seen, cefuroxime axetil had no effects on behaviour or pupil diameter in the mouse or the rat or on gastrointestinal propulsion in the rat. Cefuroxime axetil administered orally to dogs produced no acute effects on blood pressure, heart rate, or the electrocardiogram.
10.3. Pharmacokinetics
Human
The bioavailability of cefuroxime tablets was investigated in a six-way crossover study with each of 12 male adult volunteers receiving a single intravenous dose of cefuroxime sodium and five oral doses of cefuroxime axetil. Blood samples were collected at specified intervals for 12h and urine for 24h following each dose. The results of this study are presented in Table 4.
Table 4: Pharmacokinetics of Cefuroxime axetil Administered as cefuroxime axetil tablets to adults
| Dose (mg) | Route | Fasted/ Fed | Peak Serum Concentra tion (mcg/mL) | Time to peak (h) | Area Under Serum Level-Time Curve (mg·h/L) | Urine Recovery 0 to 12 h (mg) | % Dose recovered in urine | % Dose Absorbed Relative to I.V. | Half-life (h) |
| 500 | i.v. | fasted | 53.2 | 0.1 | 52.8 | 415 | 83 | 100 | 1.3 |
| 500 | po | fasted | 4.9 | 2.3 | 18.9 | 161 | 32 | 36 | 1.6 |
| 125 | po | fed | 2.1 | 2.2 | 6.7 | 65 | 52 | 51 | 1.2 |
| 250 | po | fed | 4.1 | 2.5 | 12.9 | 127 | 51 | 49 | 1.2 |
| 500 | po | fed | 7.0 | 3.0 | 27.4 | 242 | 48 | 52 | 1.2 |
| 1000 | po | fed | 13.6 | 2.5 | 50.0 | 434 | 43 | 47 | 1.3 |
The mean values of pharmacokinetic parameters after 12 volunteers received a single i.v. dose of cefuroxime and 5 oral doses of cefuroxime axetil.
Increasing doses of cefuroxime produced linear increases in peak serum concentrations and AUC.
Bioavailability appears to be independent of dose but is increased by the presence of food. Absolute bioavailability of cefuroxime axetil tablets (500 mg dose) increased from 36% in fasted subjects to 52% after food.
Absorption
The half-life of cefuroxime following oral administration to healthy adult volunteers is 1.2 hours to 1.6 hours.
Elimination
The amount of cefuroxime excreted in urine over 24h averaged 83% following intravenous dosing and ranged from 43% to 45% following oral dosing when taken after food.
Special Populations and Conditions
- Renal Insufficiency:
Cefuroxime pharmacokinetics have been investigated in patients with various degrees of renal impairment. Cefuroxime elimination half-life increases with decrease in renal function which serves as the basis for dosage adjustment recommendations in this group of patients (see 4.2. Recommended Dose and Dosage Adjustment). In patients undergoing haemodialysis, at least 60% of the total amount of cefuroxime present in the body at the start of dialysis will be removed during a 4-hour dialysis period. Therefore, an additional single dose of cefuroxime should be administered following the completion of haemodialysis.
- 11. Storage, Stability, and Disposal
Store at room temperature 15°C-30°C. Keep in tightly closed container.
Keep out of reach and sight of children.
APO-CEFUROXIME should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Cefuroxime axetil
Chemical name: (RS) 1-Hydroxyethyl (6R, 7R)-7[2-(2-furyl) glyoxylamido]-3-hydroxymethyl)-8-oxo-5-thia-1-azabicyclo [4.2.0] oct-2-ene-2-carboxylate, 72-(Z)-(0-methyl-oxime), 1-acetate 3-carbamate.
Molecular formula and molecular mass: C20H22N4O10S / 510.5 g/mol.
Structural formula:
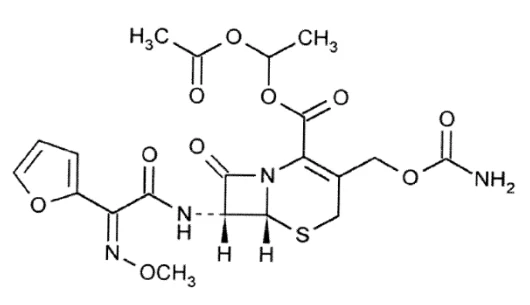
Physicochemical properties: Cefuroxime axetil is an amorphous white to cream-coloured powder. It is soluble in dimethyl sulfoxide, dimethylformamide, 1,4-dioxan, chloroform, acetone, glacial acetic acid, ethyl acetate, and methanol.
It is soluble with decomposition in 2N sodium hydroxide and slightly soluble in water, diethyl ether, 95% ethanol, and toluene, and insoluble in 2N hydrochloric acid. Cefuroxime axetil decomposes below its melting point.
14. Clinical Trials
14.2. Comparative Bioavailability Studies
A randomized, two-way, single dose (500 mg dose as 1 x 500 mg), crossover, comparative oral bioavailability study of APO-CEFUROXIME tablet (Apotex Inc.) and CEFTIN® tablet (GlaxoSmithKline Inc.) was conducted in healthy, adult, male and female subjects under fasting conditions. Comparative bioavailability data from the 16 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Cefuroxime (1 x 500 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (mcg·h/mL) | 20.58 21.51 (31.67) | 19.38 20.29 (33.42) | 106.2 | 99.0 – 113.9 |
AUCI (mcg·h/mL) | 21.14 22.09 (31.36) | 19.94 20.84 (33.84) | 106.0 | 98.9 – 113.7 |
Cmax (mcg/mL) | 6.25 6.52 (31.09) | 6.16 6.30 (22.35) | 101.3 | 91.0 – 112.9 |
Tmax3 (h) | 1.75 (1.00- 5.00) | 1.50 (1.25 - 3.50) | ||
T½4 (h) | 1.26 (13.42) | 1.29 (11.30) | ||
1 APO-CEFUROXIME (cefuroxime as cefuroxime axetil) tablets, 500 mg (Apotex Inc.) 2 PrCEFTIN® (cefuroxime as cefuroxime axetil) tablets, 500 mg (GlaxoSmithKline Inc.) 3 Expressed as the median (range) only 4 Expressed as the arithmetic mean (CV%) only | ||||
15. Microbiology
Cefuroxime has been demonstrated to be active against various susceptible strains of the following microorganisms both in vitro and in clinical infections (see 1. Indications).
Aerobic Gram-Positive Microorganisms:
Staphylococcus aureus (methicillin susceptible)
Streptococcus pneumoniae
Streptococcus pyogenes (including group A beta-hemolytic streptococci)
Streptococcus agalactiae
Aerobic Gram-Negative Microorganisms:
Haemophilus influenzae (including beta-lactamase negative, beta-lactamase positive and ampicillin-resistant strains)
Haemophilus parainfluenzae
Klebsiella pneumoniae
Moraxella catarrhalis
In vitro susceptibility data is available for the following microorganisms.
Aerobic Gram-Positive Microorganisms:
Staphylococcus aureus (methicillin susceptible)
Coagulase negative Staphylococcus spp (methicillin susceptible)
Streptococcus agalactiae
Streptococcus pneumoniae (including penicillin-susceptible, -intermediate and –resistant strains)
Streptococci spp.-β-haemolytic
Streptococcus pyogenes
Aerobic Gram-Negative Microorganisms:
Citrobacter freundii
Enterobacteriaceae
Enterobacter spp.
Escherichia coli
Haemophilus influenza (including beta-lactamase negative and positive strains)
Haemophilus parainfluenzae
Klebsiella oxytoca
Klebsiella pneumoniae
Klebsiella spp.
Moraxella catarrhalis
Morganella morganii
Proteus mirabilis
Providencia spp.
Anaerobes
Bacteroides spp.
Clostridium spp.
Fusobacterium nucleatum/necrophorum
Peptostreptococcus micros
Susceptibility Testing:
The results of susceptibility testing, by either disk-diffusion or broth microdilution techniques, should be interpreted according to the criteria established in CLSI M-100 S24 document as shown in Table 5. Quality control (QC) should be performed and evaluated according to CLSI published QC ranges as shown in Table 6.
Table 5: Disk and MIC breakpoints for cefuroxime susceptibility testing
| Organism | Zone Diameter Interpretive Criteria* (mm) (30 mcg disk) | MIC Interpretive Criteria* (mcg/mL) | ||||
|---|---|---|---|---|---|---|
| Sensitive | Intermediate | Resistant | Sensitive | Intermediate | Resistant | |
| Hemophilus influenzae | ≥20 | 17 - 19 | ≤16 | ≤4 | 8 | ≥16 |
| Enterobacteriace ae | ≥23 | 15 - 22 | ≤14 | ≤4 | 8 - 16 | ≥32 |
| Staphylococcus spp. | Note 1 | Note 1 | ||||
| Streptococcus pneumoniae | - | - | - | ≤1 | 2 | ≥4 |
| Streptococcus pyogenes | Note 2 | Note 2 | ||||
*Interpretive criteria based on CLSI M100-S24 interpretive criteria
1Oxacillin-resistant S. aureus and coagulase-negative staphylococci are considered resistant to cefuroxime
2Penicillin-susceptible S. pyogenes can be considered susceptible to cefuroxime
Table 6: Disk and MIC QC ranges for cefuroxime susceptibility testing
| QC Strain | Disk Range* (mm) | MIC Range* (mcg/mL) |
|---|---|---|
| QC Strain | Disk Range* (mm) | MIC Range* (mcg/mL) |
| Escherichia coli ATCC 25922 | 20 - 26 | 2 - 8 |
| Haemophilus influenzae 49766 | 28 - 36 | 0.25 - 1 |
| Staphylococcus aureus ATCC 25923 | 27 - 35 | - |
| Staphylococcus aureus ATCC 29213 | - | 0.5 - 2 |
| Streptococcus pneumoniae ATCC 49619 | - | 0.25 - 1 |
*Disk and MIC QC ranges published from CLSI M100-S24
16. Non-Clinical Toxicology
General toxicology
Acute Toxicity:
The experimental details of single-dose toxicity studies are presented in Table 7.
Table 7: Acute Toxicity
| Animal | Age | Route | Doses (g/kg) | Animals /Dose* | Length Of Observation | LD50 (g/kg) |
| mouse | adult | p.o. | 0.6 | 20 | 3 days | >6 |
| mouse | adult | p.o. | 0.6 | 20 | 14 days | >6 |
| mouse | adult | p.o. | 6 | 20 | 14 days | >6 |
| mouse | adult | p.o. | 1.5, 3 | 12 | 14 days | >6 |
| rat | adult | p.o. | 0, 6 | 12 | 3 days | >6 |
| rat | adult | p.o. | 0, 6 | 12 | 14 days | >6 |
| rat | adult | p.o. | 6 | 12 | 14 days | >6 |
| rat | 10 days | p.o. | 0, 3 | 20 | 3 days | >3 |
| rat | 10 days | p.o. | 0, 3 | 20 | 14 days | >3 |
| rat | adult | s.c. | 1.5, 3 | 12 | 14 days | >3 |
| dog | 8 - 10 mo. | p.o. | 1.5, 3 | 4 | 14 days | >3 |
* Each dosage group was composed of equal numbers of males and females
All animals survived the experiments. The median lethal dose of cefuroxime axetil in these animals is therefore, in excess of the test doses administered.
The only symptom of systemic toxicity observed was a temporary reduction in body weight in the juvenile (10-day-old) rats. All other animals remained apparently healthy during the observation period.
Mice and rats were sacrificed following the observation period. Histological examination of major organs and tissues revealed no evidence of systemic toxicity.
Subcutaneous injections in mice and rats caused local swelling due to the accumulation of large volumes of suspension. Small localized subcutaneous accumulations of test compound with slight peripheral tissue reaction were observed at autopsy.
Compacted test material was still present in the stomachs of most mice and rats three days after oral dosing. Inflammatory changes observed in the stomach walls of several animals were considered to be due to the mechanical irritation caused by these masses.
Long Term Toxicity:
In subacute and chronic studies in rats receiving high oral doses of cefuroxime axetil (1.0 to 2.5 g/kg/day), accumulation of drug substance and the formation of concretions in the stomachs of many animals caused high rates of mortality. The concretions consisted of semicrystalline axetil, water, food, polymers and impurities comparable to that in the administered material.
Concretions were not a problem in the dog studies, which all proceeded to completion. Experimental details of subacute and chronic toxicity studies are presented in Table 8.
Table 8: Subacute and Chronic Toxicity
| Animal | Ages* | Route | Daily Doses (g/kg) | Animals/ Dose** | Intended Duration Of | |
| Treatment | Recovery | |||||
rat rat rat | 7-9 wk 7-9 wk 7-9 wk | p.o. p.o. p.o. | 0, 0.1, 0.4, 0.8, 1.7, 2.5 | 12 12 12 | 15 wk 15 wk 15 wk | - 22 days - |
rat rat | 8-10 wk 9 wk | p.o. p.o. | 0, 0.1, 0.4, 1.6 0, 0.15, 0.4, 1.0 | 60 30 | 28 wk 90 days | - - |
rat rat rat | 7 wk 7 wk 7 wk | p.o. p.o. p.o. | 0, 0.1, 0.4, 1.0 | 32 24 12 | 28 wk 28 wk 31 wk | - 5 wk - |
| dog | 12-16 wk | p.o. | 0, 0.1, 0.2, 0.4, 0.8 | 6 | 5 wk | - |
| dog | 8 mo | p.o. | 0, 0.15, 0.4, 1.0 | 8 | 90 days | - |
dog dog | 4.5-6 mo 4.5-6 mo | p.o. p.o. | 0, 0.1, 0.4, 1.6 0, 0.4 | 8 4 | 27 wk 27 wk | - 3 wk |
* Ages at commencement of treatment. ** Each dosage group was composed of equal numbers of males and females.
Rat: 5-week study
There were no adverse effects related to treatment in the 0.1 and 0.4 g/kg groups.
By the end of the study, males in the 0.8 and 1.7 g/kg groups exhibited increased clotting times. An increase in serum alkaline phosphatase levels was seen in male rats in the 1.7 g/kg group. Histological changes in the stomach wall, similar to those seen in animals on 2.5 g/kg/day, were observed in males and females in the 1.7 g/kg group, and were considered to be primarily a consequence of the mechanical effects of drug accumulation.
In the high-dose (2.5 g/kg) group, all of the males were killed on day 9 and three of the females were killed or died later during the study. The deaths followed clinical deterioration due to accumulation of drug ester in the stomach. In affected rats there was thrombocytopenia in most cases and a slightly prolonged plasma-activated partial thromboplastin time in one case. Histological examination revealed mechanical damage to the stomach wall, and in one case there was scattered renal tubular eosinophilia and desquamation.
Rat: 90 day study
A number of rats died during the study; macroscopic and microscopic examination confirmed that these deaths were not related to cefuroxime axetil. The general condition of the surviving animals remained satisfactory throughout the study and the treatment did not affect the normal increase in body weight.
There was a slight decrease in total leukocyte counts observed in all dosage groups, resulting from a reduction in the number of neutrophils and lymphocytes and probably due to the protective effect of the test compound against those microbes that may influence leukocyte homeostasis.
A reversible decrease in plasma coagulation activity occurred in males, predominantly in the high-dose (1.0 g/kg) group. This may have been due to a direct action of cefuroxime axetil on the coagulation system or to reduced synthesis of coagulation factors as a result of suppression of Vitamin K-producing organisms in the intestine.
Rat: 28-week study
Rats in the 0.1 and 0.4 g/kg groups showed no significant toxicity and were in good general condition when the study was terminated after 62 to 65 days of treatment. However, the animals given 1.6 g/kg/day suffered from gastrointestinal trauma resulting from the mechanical effects of firm agglomerates of cefuroxime ester. Despite reduction of their dose to 1.0 g/kg/day on Day 7, they continued to deteriorate and either died or were killed after 10 to 14 days treatment.
In a further 28 week study in rats, there were no deaths attributable to any toxic effect of cefuroxime axetil.
Apart from loose faeces, seen mainly during the first six weeks of the study in animals receiving 0.4 and 1.0 g/kg/day, there were no significant effects on the general condition of rats surviving to the end of the study. Salivation, extension of the forearms, and walking on the toes was observed in treated animals at the time of dosing, but were considered to be primarily a response to the dosing procedures rather than a toxic effect of the drug.
A reduction in leukocyte counts was observed in all treatment groups, probably reflecting a protective action of the antibiotic against minor infections. Other laboratory abnormalities observed included lengthened clotting times in males, reduction in AST and ALT, and increases in serum transaminases in a few individual females without histological evidence of hepatic damage.
At the end of the treatment period, 48% of the animals in the high-dose (1.0 g/kg) group had agglomerates of cefuroxime axetil in the stomach at autopsy, with one subject exhibiting an associated inflammation of the stomach wall.
Dog: 5-week study
Apart from a single case of vomiting shortly after dosing, the general condition of the dogs was not adversely affected by the treatment.
Laboratory abnormalities observed included transient decreases in total leukocyte and neutrophil counts, hyponatremia, and increased inorganic phosphorus and triglyceride levels. None of the individual results were sufficiently abnormal to be of clinical significance and there were no histological changes associated with treatment.
Dog: 90-day study
The general condition of the animals remained satisfactory throughout the study with normal increases in body weight attained. Isolated and occasional vomiting was the only apparent adverse effect, but this response can partly be attributed to the oral intubation.
Increases in erythrocyte sedimentation rate and in leukocyte and eosinophil counts were observed in animals with incidental helminthic infections. Females in the 0.4 and 1.0 g/kg groups exhibited increased total serum iron binding capacity. There is a statistically significant decrease in the absolute weights of livers in males and hearts in females in the 0.4 g/kg group, but this is insignificant when related to total body weights.
Dog: 27-week study
The general condition of the animals remained satisfactory throughout the study with the exception of 3 dogs, 2 of which were sacrificed suffering from illnesses unrelated to treatment.
In the high-dose (1.6 g/kg/day) group salivation and vomiting were noted, and in one dog there was a transient reduction in growth rate and a general loss of condition. Laboratory abnormalities included reduced erythrocyte counts, prolonged clotting times, reduction in plasma protein and cholesterol, and an increase in plasma triglyceride. Post mortem examinations revealed no signs of organ toxicity.
Nephrotoxicity Studies:
Single Dose Administration
Mouse
Mice received single subcutaneous doses of cefuroxime sodium (10 g/kg) alone or in combination with furosemide (50 mg/kg) or furosemide plus glycerol 5.4 mL/kg. Cefuroxime alone caused no nephrotoxicity; when administered concomitantly with furosemide there was proximal tubular necrosis in 2 out of 9 animals. The combination of furosemide and glycerol caused tubular necrosis in 5 of 8 animals but this was not influenced by the addition of cefuroxime.
Rat
Cefuroxime sodium at doses up to 10 g/kg was administered either alone or in combination with furosemide (100 mg/kg) or furosemide plus glycerol (3.15 mL/kg). Three of 6 animals exhibited proximal tubular necrosis in the inner cortex following administration of 4 g of cefuroxime alone. The incidence and severity of necrosis increased with increasing doses of cefuroxime. The incidence of tubular necrosis also increased when furosemide or furosemide plus glycerol were given concomitantly. Cefuroxime at 1g/kg enhanced the severity of the furosemide-glycerol-induced necrosis in the outer cortex. Treatment with furosemide plus glycerol also lowered the dosage of cefuroxime to 2 g/kg required to produce necrosis of the inner cortex.
Rat: Repeated dose study
Rats received cefuroxime at doses ranging from 1 to 5 g/kg/day subcutaneously for 10 days. There was no histological evidence of tubular necrosis at 5 g/kg, but transient increases in urine volume, protein and enzymes, which peaked at day 2 to 3 were observed. The body weights of the animals were significantly reduced for the high dose group.
Combination with aminoglycosides
Rats were treated with gentamicin (35 mg/kg) for 10 days. Cefuroxime sodium was given either concomitantly during the 10 days or as a single dose with the ninth dose of gentamicin. Gentamicin-induced tubular necrosis was not potentiated by the administration of single doses of cefuroxime up to 6 g/kg/day. Multiple doses of cefuroxime up to 4 g/kg protected rats against gentamicin-induced nephrotoxicity, but at doses of 6 g/kg/day of cefuroxime, severe tubular necrosis was observed after 4 days of treatment. Similar results were found with amikacin and tobramycin.
Genotoxicity
Several standard assays were done to assess the mutagenic properties of cefuroxime axetil. These included both in vitro (Ames test, fluctuation test, gene conversion assay) and in vivo (micronucleus tests) assays.
In vitro assays: Cefuroxime axetil was subjected to standard Ames tests, fluctuation tests, and gene conversion tests in concentrations of up to 208 mcg/plate, 8.3 mcg/mL, and 833 mcg/mL respectively. The results of these tests were negative. Negative results were also obtained at high concentrations (833 mcg/mL) in a modified fluctuation test in which the test strains were rendered resistant to cefuroxime's antibacterial properties. A weak, but statistically significant response was observed at 416 mcg/mL, but this was not regarded as biologically significant since no effect was detected at 833 mcg/mL.
In vivo micronucleus test: Groups of five male mice received oral doses of cefuroxime axetil equivalent to 1.486, 1.114, 0.743 and 0.372 g/kg cefuroxime. Negative control groups received vehicle only and positive controls were dosed with 100 mg/kg cyclophosphamide. At either 24 or 48h, groups of animals were killed and the bone marrow of both femurs collected. Smears were prepared and examined for micronuclei.
There was no significant increase in the proportion of polychromatic erythrocytes with micronuclei in any of the groups treated with cefuroxime axetil when compared with their negative control at either expression time.
The ratios of mature to immature erythrocytes observed in animals receiving cefuroxime axetil were not significantly different from the negative controls at either expression time.
Reproductive and developmental toxicology
Rodents
The reproductive toxicity of oral cefuroxime axetil was investigated in rats and mice as summarized in Table 9.
Table 9: Reproduction and Teratology Studies
| Animal | Sex | Doses (mg/kg/day) | Animals/ Dose | Duration Of Treatment | Significant Observations* |
| mouse | F | 0, 150, 500, 1600 | 30** | day 7 to day 16 of pregnancy | decreased number of implants (F0) increased F1 male: female ratio |
| rat | F | 0, 125, 250, 500 | 20 | day 17 of pregnancy to day 21 post partum | delayed pinna detachment (F1 females) |
| rat | M | 0, 125, 250, 500 | 10 | 70 days prior to mating | delayed F1 mating, increased F2 male: female ratio, delayed primary coat (F2 females), delayed eye opening (F2 males), delayed pinna detachment (F2) |
| F | 0, 125, 250, 500 | 30** | 21 days before mating to day 21 post partum | ||
| rat | F | 0, 125, 250, 500 | 30*** | day 7 to day 16 of pregnancy | decreased number of implants (F0), decreased number of live F1 fetuses |
* Apparent reproductive toxicity (i.e. other than F0 organ toxicity) which was dose related and not due to experimental artifacts or to the antimicrobial action of the drug (e.g. suppression of intestinal microflora).
** 20 animals were killed at term; 10 were allowed to litter and complete the treatment.
*** 15 animals were killed at term; 15 were allowed to litter and complete the treatment.
The most common gross abnormality observed in offspring of treated dams was hydronephrosis, seen in comparable numbers at all dose levels including controls. There was no evidence that cefuroxime axetil had adversely affected fertility or peri-/post-natal development or organogenesis in rats or mice.
Rabbit
Rabbits were found to be unsuitable for reproductive toxicity testing of cefuroxime axetil. Six unmated females were treated with daily doses of 0.1 to 0.5 g/kg while 6 mated females received 0.2 g/kg. All but one animal showed a chronic loss of body weight and deterioration in overall conditions (3 animals died). One of the mated animals maintained a viable pregnancy.
Two aborted and evidence of earlier resorption of implants was found in another two.
Post mortem examination of rabbits in both groups revealed liquified intestinal contents and distended, gas-filled caecums in many cases. Changes in intestinal microflora were thought to be the cause of the observed toxicity.
Special toxicology
Tolerance Studies: Cefuroxime axetil, applied as a 50% suspension in soft paraffin/liquid paraffin to intact and abraded guinea pig skin under occlusive dressing for 21 hours, produced negligible irritancy. Cefuroxime axetil was strongly sensitizing when applied to guinea pig skin. Sixteen days after application of sensitizing doses to 10 animals, challenge with the test material produced a positive erythematous response in 9 animals after 24 hours and in all 10 after 48 hours.
17. Supporting Product Monographs
- 1. CEFTIN® (Cefuroxime axetil for oral suspension, Granules for suspension USP, 125 mg/5 mL), control 297795, Product Monograph, Sandoz Canada Inc. (2025-10-03)