


Product Monograph - Apo-Vortioxetine
RECENT MAJOR LABEL CHANGES
Not Applicable.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
TABLE OF CONTENTS ................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
1 INDICATIONS .................................................................................................................... 4
1.1 Pediatrics.................................................................................................................... 4
1.2 Geriatrics .................................................................................................................... 4
2 CONTRAINDICATIONS ....................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................................. 5
4 DOSAGE AND ADMINISTRATION ...................................................................................... 5
4.1 Dosing Considerations ............................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .......................................................... 5
4.2.1 Discontinuing Treatment ........................................................................................... 7
4.3 Reconstitution ............................................................................................................ 7
4.4 Administration ........................................................................................................... 7
4.5 Missed Dose ............................................................................................................... 7
5 OVERDOSAGE ................................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ...................................... 8
7 WARNINGS AND PRECAUTIONS ........................................................................................ 9
7.1 Special Populations .................................................................................................. 14
7.1.1 Pregnant Women ..................................................................................................... 14
7.1.2 Breast-feeding .......................................................................................................... 15
7.1.3 Pediatrics.................................................................................................................. 15
7.1.4 Geriatrics .................................................................................................................. 15
8 ADVERSE REACTIONS ....................................................................................................... 16
8.1 Adverse Reaction Overview ..................................................................................... 16
8.2 Clinical Trial Adverse Reactions................................................................................ 16
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ............................................................ 22
8.3 Less Common Clinical Trial Adverse Reactions ........................................................ 23
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ..................................................................................................... 25
8.5 Post-Market Adverse Reactions ............................................................................... 25
9 DRUG INTERACTIONS ...................................................................................................... 26
9.1 Serious Drug Interactions ........................................................................................... 26
9.2 Drug Interactions Overview........................................................................................ 26
9.3 Drug-Behavioural Interaction ..................................................................................... 28
9.4 Drug-Drug Interactions ............................................................................................... 28
9.5 Drug-Food Interactions .............................................................................................. 31
9.6 Drug-Herb Interactions ............................................................................................... 31
9.7 Drug-Laboratory Test Interactions ............................................................................. 31
10 ACTION AND CLINICAL PHARMACOLOGY ........................................................................ 32
10.1 Mechanism of Action ................................................................................................. 32
10.2 Pharmacodynamics .................................................................................................... 32
10.3 Pharmacokinetics ....................................................................................................... 32
11 STORAGE, STABILITY AND DISPOSAL ............................................................................... 35
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................. 35
PART II: SCIENTIFIC INFORMATION ........................................................................................... 36
13 PHARMACEUTICAL INFORMATION .................................................................................. 36
14 CLINICAL TRIALS ............................................................................................................... 36
14.1 Clinical Trials by Indication ......................................................................................... 36
Major Depressive Disorder .................................................................................................. 36
14.2 Comparative Bioavailability Studies ........................................................................... 40
15 MICROBIOLOGY ............................................................................................................... 42
16 NON-CLINICAL TOXICOLOGY ............................................................................................ 42
17 SUPPORTING PRODUCT MONOGRAPHS .......................................................................... 45
PATIENT MEDICATION INFORMATION ...................................................................................... 46
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-VORTIOXETINE (vortioxetine tablets) is indicated for:
- the treatment of major depressive disorder (MDD) in adults.
The efficacy of vortioxetine tablets in providing symptomatic relief of MDD was demonstrated in double-blind, placebo-controlled clinical trials of up to 8 weeks duration (see 14.1 Clinical Trials by Indication, Study Results).
The efficacy of vortioxetine tablets in maintaining an antidepressant response for up to 24 weeks was demonstrated in a double-blind, placebo-controlled trial in patients with MDD who initially responded to 12-weeks of acute, open label treatment with vortioxetine tablets (see 14.1 Clinical Trials by Indication, Study Results).
Physicians who elect to use APO-VORTIOXETINE for extended periods should periodically re-evaluate the usefulness of the drug for individual patients.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of vortioxetine tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm; 7.1.3 Pediatrics and 8.2.1 Clinical Trial Adverse Reactions – Pediatrics).
1.2 Geriatrics
Geriatrics (≥65 years of age): The lowest effective dose of 5 mg/day should always be used as the starting dose in elderly patients (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal, Bone Fracture Risk, and Renal, Hyponatraemia 7.1.4 Geriatrics; 4.2 Recommended Dose and Dosage Adjustment, Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions; and 14.1 Clinical Trials by Indication, Study Results).
2 CONTRAINDICATIONS
APO-VORTIOXETINE is contraindicated in:
- patients who are hypersensitive to vortioxetine or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. Angioedema has been reported in patients treated with vortioxetine tablets. For a complete listing of excipients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
patients with concomitant use of monoamine oxidase inhibitors (MAOIs) (see 9.2 Drug
- Overview; 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Toxicity/Neuroleptic Malignant Syndrome).
Monoamine Oxidase Inhibitors (MAOIs)
Vortioxetine increases serotonergic neurotransmission and must not be used concomitantly in patients taking MAOIs, including linezolid, an antibiotic, methylene blue, a dye used in certain surgeries, or in patients who have taken MAOIs within the preceding 14 days due to the risk of serious, sometimes fatal, drug interactions. These interactions have been associated with symptoms that include tremor, myoclonus, diaphoresis, nausea, vomiting, flushing, dizziness, hyperthermia with features resembling neuroleptic malignant syndrome or serotonin toxicity, seizures, rigidity, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes that include extreme agitation progressing to delirium and coma. Therefore, at least 14 days should be allowed after discontinuing treatment with a MAOI before starting treatment with vortioxetine.
At least 21 days should elapse after discontinuing vortioxetine treatment before starting a MAOI (see 9.2 Drug Interactions Overview).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- APO-VORTIOXETINE is not indicated for use in patients below the age of 18 (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
4.2 Recommended Dose and Dosage Adjustment
Adults
The starting and recommended dose of APO-VORTIOXETINE is 10 mg vortioxetine once daily for adults less than 65 years of age. Depending on individual patient response, the dose may be increased to a maximum of 20 mg vortioxetine once daily, as tolerated. A dose decrease to a minimum of 5 mg vortioxetine once daily may be considered for patients who do not tolerate higher doses.
In clinical trials conducted outside the United States, efficacy was demonstrated with 5 mg/day, 10 mg/day, 15 mg/day and 20 mg/day. In the clinical trials conducted in the United States, efficacy was demonstrated with 20 mg/day vortioxetine tablets (see 14.1 Clinical Trials by Indication, Study Results). The efficacy and safety of doses greater than 20 mg/day were not evaluated in controlled clinical trials.
It is generally agreed that acute episodes of major depression require several months or longer of sustained pharmacologic therapy beyond response to the acute episode (see 14.1 Clinical Trials by Indication, Study Results). During long-term therapy, the dosage should be maintained at the lowest effective level and patients should be periodically reassessed to determine the need to continue treatment.
- Pediatrics (<18 years of age)
Health Canada has not authorized an indication for pediatric use.
- Geriatrics (>65 years of age)
The lowest effective dose of 5 mg/day vortioxetine should always be used as the starting dose for patients of 65 years of age or older. Caution is advised when treating elderly patients with doses greater than 10 mg/day due to the limited efficacy and safety data from patients of 65 years of age or older that were treated with these doses in controlled clinical trials (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal, Bone Fracture Risk and Renal, Hyponatraemia; 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics; and 14.1 Clinical Trials by Indication, Study Results).
Dosage Adjustment
Patients with Renal Impairment
No dose adjustment is recommended for patients with renal impairment or for patients with end- stage renal disease. However, as with any medicine, caution should be exercised when treating patients with severe renal insufficiency (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Patients with Hepatic Impairment
No dose adjustment is recommended for patients with hepatic impairment. However, due to extensive hepatic metabolism of vortioxetine, caution is advised when APO-VORTIOXETINE is prescribed in patients with moderate or severe hepatic impairment (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Cytochrome P450 Inhibitors
Reduce the dose of APO-VORTIOXETINE by half if strong CYP2D6 inhibitors (e.g. bupropion, quinidine, fluoxetine, paroxetine) are added to APO-VORTIOXETINE treatment (see 9.4 Drug- Drug Interactions).
Cytochrome P450 Inducers
Depending on individual patient response, a dose adjustment of APO-VORTIOXETINE may be considered if a broad cytochrome P450 inducer (e.g. rifampicin, carbamazepine, phenytoin) is added to APO-VORTIOXETINE treatment (see 9.4 Drug-Drug Interactions).
4.2.1 Discontinuing Treatment
Although vortioxetine tablets have a relatively long elimination half-life, abrupt discontinuation in placebo-controlled trials was associated with discontinuation symptoms (see 8.2 Clinical Trial Adverse Reactions, Discontinuation Symptoms). Patients should be monitored for discontinuation symptoms when discontinuing treatment with APO-VORTIOXETINE. A gradual reduction in the dose, rather than an abrupt cessation, is recommended whenever possible.
When discontinuing APO-VORTIOXETINE, the impact of the elimination half-life of vortioxetine tablets (mean elimination half-life of 66 hours) should be considered when drugs that might interact with APO-VORTIOXETINE are prescribed (see 9 DRUG INTERACTIONS and 10.3 Pharmacokinetics, Elimination).
4.3 Reconstitution
Not Applicable.
4.4 Administration
APO-VORTIOXETINE should be administered as a single daily dose, with or without food.
4.5 Missed Dose
If a dose is missed, the next dose should be taken at the usual time. Patients should not take a double dose to make up for a missed dose.
5 OVERDOSAGE
In pre-market clinical studies, the maximum single dose tested was 75 mg in men. Cases of overdose were limited to patients who accidentally or intentionally consumed up to a maximum dose of 40 mg of vortioxetine tablets for up to 4 days. In clinical studies that included healthy subjects, ingestion of vortioxetine 40 mg to 75 mg was associated with increased incidences of nausea, postural dizziness, diarrhoea, abdominal discomfort, generalized pruritus, somnolence and flushing.
Post-marketing experience mainly concerns vortioxetine overdoses of up to 80 mg. In the majority of cases, no symptoms or mild symptoms were reported. The most frequently reported symptoms were nausea and vomiting.
There is limited experience with vortioxetine overdoses above 80 mg. Following dosages several fold higher than the therapeutic dose range, events of seizure and serotonin toxicity have been reported.
Management of overdose should consider the possibility of multiple drug involvement and should consist of treatment of clinical symptoms and relevant monitoring. Medical follow-up in a specialized environment is recommended.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet 5 mg, 10 mg, 15 mg, 20 mg | Dibasic calcium phosphate, magnesium stearate, mannitol, propyl gallate, polyvinyl alcohol, polyethylene glycol, red ferric oxide (5 mg, 15 mg and 20 mg), sodium starch glycolate, talc, titanium dioxide, yellow ferric oxide. |
Each APO-VORTIOXETINE tablet contains 6.36 mg, 12.71 mg, 19.07 mg, or 25.42 mg of vortioxetine hydrobromide equivalent to 5 mg, 10 mg, 15 mg, or 20 mg of vortioxetine, respectively.
Film-coated tablet.
5 mg: Pink, almond shape, biconvex coated tablet. Engraved "APO" on one side, "VO5" on the other side
10 mg: Yellow, almond shape, biconvex coated tablet. Engraved "APO" on one side, "VO10" on the other side.
15 mg: Orange, almond shape, biconvex coated tablet. Engraved "APO" on one side, "VO15" on the other side.
20 mg: Red, almond shape, biconvex coated tablet. Engraved "APO" on one side, "VO20" on the other side.
Bottle: Pack size of 100.
7 WARNINGS AND PRECAUTIONS
Dependence/Tolerance
Although vortioxetine has not been systematically studied for its potential for abuse, there was no indication of drug-seeking behaviour in clinical trials with vortioxetine tablets. Physicians should carefully evaluate patients for history of drug abuse and follow such patients closely, observing them for signs of misuse or abuse of APO-VORTIOXETINE.
Discontinuation Symptoms
Abrupt discontinuation of vortioxetine tablets in placebo-controlled trials was associated with discontinuation symptoms (see 8.2 Clinical Trial Adverse Reactions, Discontinuation Symptoms). Patients should be monitored for discontinuation symptoms when discontinuing treatment with APO-VORTIOXETINE. A gradual reduction in the dose, rather than an abrupt cessation, is recommended whenever possible (see 4.2.1 Discontinuing Treatment). Adverse reactions particularly after abrupt discontinuation of serotonergic antidepressants include: nausea, sweating, dysphoric mood, irritability, agitation, dizziness, sensory disturbances (e.g., paresthesia, such as electric shock sensations), tremor, anxiety, confusion, headache, lethargy, emotional lability, insomnia, hypomania, tinnitus, and seizures.
Driving and Operating Machinery
Patients should exercise caution when driving or operating hazardous machinery until they are reasonably certain that APO-VORTIOXETINE does not adversely affect their ability to engage in such activities (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
Hematologic
Abnormal Bleeding
SSRIs and serotonin/norepinephrine reuptake inhibitors (SNRIs), including APO-VORTIOXETINE, may increase the risk of bleeding events by causing abnormal platelet aggregation. Concomitant use of acetylsalicylic acid (ASA), nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin and other anticoagulants may add to the risk. Case reports and epidemiological studies (case-control and cohort design) have demonstrated an association between use of drugs that interfere with serotonin reuptake and the occurrence of gastrointestinal bleeding. Bleeding events related to SSRIs and SNRIs use have ranged from ecchymoses, hematomas, epistaxis, and petechiae to life-threatening hemorrhages (see 8 ADVERSE REACTIONS). Gastrointestinal and gynaecological bleeding have also been reported following treatment with vortioxetine tablets. SSRIs/SNRIs including APO-VORTIOXETINE, may increase the risk of postpartum hemorrhage (see 7.1.1 Pregnant Women).
Caution is advised in patients with a history of bleeding disorder or predisposing conditions (e.g. thrombocytopenia or coagulation disorders). Patients should be cautioned about the risk of bleeding associated with the concomitant use of APO-VORTIOXETINE and NSAIDs, ASA, or other drugs that affect coagulation (see 9.2 Drug Interactions Overview).
Hepatic/Biliary/Pancreatic
Hepatic Impairment
Based on studies conducted with vortioxetine tablets in patients with mild, moderate or severe hepatic impairment, no dose adjustment is recommended on the basis of hepatic function (see 4 DOSAGE AND ADMINISTRATION and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency). However, due to extensive hepatic metabolism of vortioxetine, caution is advised when APO-VORTIOXETINE is prescribed in patients with moderate or severe hepatic impairment.
Musculoskeletal
Bone Fracture Risk
Elderly patients, patients with osteoporosis and patients with important risk factors for bone fractures should be advised of possible adverse events which increase the risk of falls, such as dizziness and orthostatic hypotension, especially at the early stages of treatment but also soon after withdrawal.
Epidemiological studies show an increased risk of bone fractures following exposure to some antidepressants, including SSRIs and other newer antidepressants. The risks appear to be greater at the initial stages of treatment, but significant increased risks were also observed at later stages of treatment. The possibility of fracture should be considered in the care of patients treated with APO-VORTIOXETINE. Preliminary data from observational studies show association of Selective Serotonin Reuptake Inhibitors (SSRIs)/Serotonin and Norepinephrine Reuptake Inhibitors (SNRIs) and low bone mineral density in older men and women. Until further information becomes available, a possible effect on bone mineral density with long-term treatment with SSRIs and other newer antidepressants including APO-VORTIOXETINE, cannot be excluded.
Neurologic
Seizures
Seizures are a potential risk with antidepressant drugs. During short-term clinical trials in patients with Major Depressive Disorder and no history of seizure disorders, seizures were reported in <0.1% of patients that received vortioxetine tablets compared to 0% that received placebo. As with other antidepressants, APO-VORTIOXETINE should be introduced cautiously in patients who have a history of seizures or in patients with unstable epilepsy. Treatment should be discontinued in any patient who develops seizures or for whom there is an increase in seizure frequency.
Serotonin Toxicity/Neuroleptic Malignant Syndrome
On rare occasions, serotonin toxicity, also known as serotonin syndrome, has been reported with vortioxetine tablets, particular during combined use with other serotonergic drugs (see 9.2 Drug Interactions Overview, Serotonergic Medicinal Products).
Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature > 38°C and ocular clonus or inducible clonus
Neuroleptic malignant syndrome has also been rarely reported with vortioxetine tablets, particularly during combination use with neuroleptic/antipsychotic drugs. The clinical manifestations of neuroleptic malignant syndrome often overlap with those of serotonin toxicity, including hyperthermia, hypertonia, altered mental status, and autonomic instability. In contrast to serotonin toxicity, patients with neuroleptic malignant syndrome may present with “lead pipe” muscle rigidity as well as hyporeflexia.
The concomitant use of APO-VORTIOXETINE with monoamine oxidase inhibitors, including linezolid and methylthioninium chloride (methylene blue), is contraindicated (see 2 CONTRAINDICATIONS, Monoamine Oxidase Inhibitors (MAOIs)). APO-VORTIOXETINE should be used with caution in patients receiving other serotonergic drugs and antipsychotics/neuroleptics. If concomitant treatment with APO-VORTIOXETINE and other serotonergic drugs and/or antipsychotics/neuroleptics is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.2 Drug Interactions Overview, Serotonergic Medicinal Products). Serotonin toxicity and neuroleptic malignant syndrome may result in potentially life-threatening conditions. If serotonin toxicity or neuroleptic malignant syndrome is suspected, discontinuation of APO-VORTIOXETINE should be considered.
Cognitive and Motor Disturbances
In a study of 21 healthy subjects who were administered single and multiple doses of 10 mg/day vortioxetine tablets in the evening, there was no significant impairment, relative to placebo, in mean parameters of driving performance, cognitive function or other psychomotor skills using a battery of neuropsychological tests on the following morning. However, some individuals may show impairment after taking APO-VORTIOXETINE (see 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery).
Ophthalmologic
Angle-Closure Glaucoma
As with other antidepressants, APO-VORTIOXETINE can cause mydriasis, which may trigger an angle- closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Psychiatric
Potential Association with Behavioural and Emotional Changes, Including Self-Harm
Pediatrics: Placebo-Controlled Clinical Trial Data
- Recent analyses of placebo-controlled clinical trial safety databases from Selective Serotonin Reuptake Inhibitors (SSRIs) and other newer antidepressants suggest that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo.
- The small denominators in the clinical trial database, as well as the variability in placebo rates, preclude reliable conclusions on the relative safety profiles among these drugs.
Adults and Pediatrics: Additional data
- There are clinical trials and post-marketing reports with SSRIs and other newer antidepressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm and harm to others. The agitation-type events include: akathisia, agitation, disinhibition, emotional lability, hostility, aggression, depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages. This includes monitoring for agitation-type emotional and behavioural changes.
An FDA meta-analysis of placebo-controlled clinical trials of antidepressant drugs in adult patients aged 18 to 24 years with psychiatric disorders showed an increased risk of suicidal behaviours with antidepressants compared to placebo.
Suicide
The possibility of a suicide attempt is inherent in major depressive disorder (MDD) and may persist until significant remission occurs. Close supervision of patients should accompany initial drug therapy, and consideration should be given to the need for hospitalization of high risk patients. The smallest quantity of drug, consistent with good patient management, should be provided to reduce the risk of overdose with this drug (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
Activation of Mania/Hypomania
Mania/hypomania was reported for <0.1% (1 out of 3904) of patients treated with vortioxetine tablets in short-term Phase 2/3 trials in patients with Major Depressive Disorder. APO-VORTIOXETINE should be used with caution in patients with a history of mania/hypomania and should be discontinued in any patient entering a manic phase. A major depressive episode may be the initial presentation of bipolar disorder. Patients with bipolar disorder may be at an increased risk of experiencing manic episodes when treated with antidepressants alone. Therefore, the decision to initiate symptomatic treatment of depression should only be made after patients have been adequately assessed to determine if they are at risk for bipolar disorder.
Aggression/agitation
Patients treated with antidepressants, including vortioxetine, may experience feelings of aggression, anger, agitation and irritability. Patient’s condition and disease status should be closely monitored. Patients (and caregivers of patients) should be alerted to seek medical advice, if aggressive/agitated behaviour emerges or aggravates.
Electroconvulsive Therapy (ECT)
The safety and efficacy of the concurrent use of vortioxetine tablets and ECT have not been studied, and therefore, caution is advisable.
Renal
Hyponatraemia
Hyponatraemia, probably due to inappropriate antidiuretic hormone secretion (SIADH), has been reported with the use of antidepressants with serotonergic effect (SSRIs, SNRIs). Caution should be exercised in patients at risk, such as elderly, cirrhotic patients, patients concomitantly treated with medications known to cause hyponatraemia (e.g. diuretics), or patients who are otherwise volume depleted. Discontinuation of APO-VORTIOXETINE should be considered in patients with symptomatic hyponatraemia and appropriate medical intervention should be instituted. Symptoms may include headache, difficulty concentrating, memory impairment, confusion, weakness, and unsteadiness, which may lead to falls.
Renal Impairment
Based on a study conducted with vortioxetine tablets in patients with mild, moderate, severe and end stage renal impairment no clinically significant pharmacokinetic changes were observed. Subsequently, no dosage adjustment is needed, however as with any medicine, caution should be exercised when treating patients with severe renal insufficiency (see 4.2 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Patients with Renal Impairment and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Reproductive Health: Female and Male Potential
Fertility
Vortioxetine had no effect on male and female rat fertility at dose levels up to 120 mg/kg/day (60 mg/kg b.i.d.) at which plasma vortioxetine concentrations were 24 and 17 times that at the MRHD (see Section 16 NON-CLINICAL TOXICOLOGY, Reproductive and Development Studies).
Function
Selective serotonin reuptake inhibitors (SSRIs), including vortioxetine, may cause symptoms of sexual dysfunction (see 8.2 Clinical Trial Adverse Reactions, Male and Female Sexual Dysfunction). Patients should be informed that there have been reports of long-lasting sexual dysfunction where the symptoms have continued despite discontinuation of SSRIs.
Teratogenic Risk
Vortioxetine was not teratogenic in rats or rabbits at dose levels up to 160 and 60 mg/kg/day, respectively (80 and 30 mg/kg b.i.d.) (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Development Studies).
7.1 Special Populations
7.1.1 Pregnant Women
The safety of vortioxetine tablets in human pregnancy has not been established. Therefore, APO-VORTIOXETINE should not be used during pregnancy or in women intending to become pregnant, unless the benefit outweighs the possible risk to the fetus.
Patients should be advised to notify their physician if they become pregnant or intend to become pregnant. If APO-VORTIOXETINE is used until or shortly before birth, discontinuation symptoms in the newborn should be considered.
Animal studies did not demonstrate a teratogenic effect of vortioxetine, but lower fetal weight and delayed ossification were seen in rats at systemic exposures corresponding to approximately 6 times the Cmax at the maximum recommended human dose (20 mg/day) and in rabbits at subtherapeutic exposures (see 16 NON-CLINICAL TOXICOLOGY).
Post-marketing reports indicate that some neonates exposed to SNRIs, SSRIs, or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included: respiratory distress, cyanosis, apnoea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycaemia, hypertonia, hypotonia, hyperreflexia, tremor, jitteriness, irritability, lethargy, constant crying, somnolence and difficulty sleeping. These symptoms are consistent with either a direct toxic effect of SNRIs, SSRIs, or other newer antidepressants, or, possibly a drug discontinuation syndrome. In a majority of instances, such complications begin immediately or soon (<24 hours) after delivery. It should be noted that, in some cases, the clinical picture is consistent with serotonin toxicity (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Toxicity/Neurologic Malignant Syndrome). When treating a pregnant woman with APO-VORTIOXETINE during later stages of pregnancy, the physician should carefully consider the potential risks and benefits of treatment.
Observational data have provided evidence of an increased risk (less than 2-fold) of postpartum hemorrhage following SSRI/SNRI exposure within the month prior to birth. Although no studies have investigated an association between vortioxetine treatment and postpartum haemorrhage, there is a potential risk, taking into account the related mechanism of action (see 7 WARNINGS AND PRECAUTIONS, Hematologic, Abnormal Bleeding)
Epidemiological studies on persistent pulmonary hypertension in the newborn (PPHN) have shown that the use of SSRIs in pregnancy, particularly use in late pregnancy, was associated with an increased risk of PPHN. PPHN occurs in 1 to 2 per 1,000 live births in the general population and is associated with substantial neonatal morbidity and mortality. In a retrospective case-control study of 377 women whose infants were born with PPHN and 836 women whose infants were born healthy, the risk for developing PPHN was approximately six-fold higher for infants exposed to SSRIs after the 20th week of gestation compared to infants who had not been exposed to antidepressants during pregnancy (Odds Ratio 6.1, 95% CI 2.2 to 16.8). A study using data from the Swedish Medical Birth Register for 831,324 infants born in 1997-2005 found an increased risk of PPHN of approximately 2-fold associated with patient-reported maternal use of SSRIs in the first trimester of pregnancy (Risk Ratio 2.4, 95% CI 1.2 to 4.3), and an increased risk of PPHN of approximately 4-fold associated with a combination of patient- reported maternal use of SSRIs in the first trimester and an antenatal SSRI prescription in later pregnancy (Risk Ratio 3.6, 95% CI 1.2 to 8.3). Although no studies have investigated the association of PPHN with vortioxetine treatment, this potential risk cannot be ruled out considering the mechanism of action (increase in serotonin concentrations).
7.1.2 Breast-feeding
Available data in animals have shown excretion of vortioxetine/vortioxetine metabolites in milk. It is expected that vortioxetine tablets will be excreted into human milk. Because a risk to the nursing child cannot be excluded, breast-feeding is not recommended during treatment with APO-VORTIOXETINE.
A decision must be made whether to discontinue breast-feeding or to discontinue/abstain from APO-VORTIOXETINE treatment, taking into account the benefit of breast-feeding for the child and the benefit of therapy for the woman.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of vortioxetine tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. Controlled clinical studies in pediatrics with major depressive disorder failed to demonstrate efficacy and do not support the use of vortioxetine tablets in the treatment of children under the age of 18 years with depression. In general, the adverse reaction profile of vortioxetine in adolescents was similar to that seen for adults, except for higher incidences of headache, vomiting, abdominal pain-related events, and in adolescents specifically, higher reports of suicidal ideation and self-harm were observed (see 7 WARNINGS AND PRECAUTIONS, Psychiatric; and 8.2.1 Clinical Trial Adverse Drug Reactions - Pediatrics).
7.1.4 Geriatrics
As with any medicine, in the context of a greater potential for other concomitant medical conditions and drug therapies in elderly patients, caution should be exercised when treating the elderly. Based on the available efficacy and safety data from placebo controlled clinical trials, a dosage adjustment is recommended for elderly patients (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics; and 14.1 Clinical Trials by Indication, Study Results).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse events information for vortioxetine tablets was collected in adult patients with MDD in a clinical programme that included more than 6,700 patients, of whom 3,460 were treated with vortioxetine tablets (5 to 20 mg/day) in short-term placebo-controlled (up to 8 weeks) studies. During clinical trials, all treatment groups were comparable with respect to gender, age and race. The mean age of patients was 46 years (18 to 88 years). Of these patients, approximately 67% were women and 33% were men.
The most commonly observed adverse events in MDD patients treated with vortioxetine tablets in 6 to 8-week placebo-controlled studies (incidence ≥5% and at least twice the rate of placebo) were nausea, constipation and vomiting. The majority of cases of nausea in the MDD Short-Term Pool were transient (median duration ranged from 9 to 16 days) and mild to moderate, but some led to discontinuation of treatment (see below). The incidence of nausea was highest during the first week of treatment. Approximately 10% of vortioxetine tablets-treated patients had nausea at the end of the 6 or 8 week treatment, compared to 2% of placebo-treated patients.
Adverse Events Leading to Discontinuation of Treatment
From the short-term (up to 8-weeks) placebo-controlled studies, discontinuation due to adverse events was more common with vortioxetine tablets (6.0%) compared with placebo (4.0%).
Nausea was the most common reason for patients discontinuing due to adverse events. In the short-term MDD placebo-controlled studies, the incidence of nausea leading to withdrawal in patients who received vortioxetine tablets 5 mg, 10 mg, 15 mg and 20 mg was 1.1%, 1.4%, 3.8% and 3.3%, respectively, compared to 0.3% for placebo. Withdrawing due to nausea was highest during the initial weeks of treatment.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Reactions in MDD Clinical Trials
Table 2 enumerates the incidence of treatment emergent adverse events that occurred in 3,460 depressed patients who received vortioxetine tablets at doses ranging from 5 to 20 mg/day in placebo-controlled trials (of up to 8 weeks in duration). Events included are those occurring in 1% or more of patients treated with vortioxetine tablets, and for which the incidence in patients treated with vortioxetine tablets was greater than the incidence in placebo-treated patients. Reported adverse events were classified using the Medical Dictionary for Regulatory Activities (MedDRA), version 14.1.
Table 2 Incidence of common adverse events* for Major Depressive Disorder, pool of 12 short-term studies | |||||
| Body System/Adverse Event | Percentage of Patients Reporting | ||||
Placebo (n = 1968) | Vortioxetine tablets 5 mg/day (n =1157) | Vortioxetine tablets 10 mg/day (n =1042) | Vortioxetine tablets 15 mg/day (n =449) | Vortioxetine tablets 20 mg/day (n =812) | |
| Gastrointestinal | |||||
| Disorders | |||||
| Nausea | 8.1 | 20.5 | 22.6 | 31.2 | 27.2 |
| Diarrhoea | 5.5 | 6.6 | 5.4 | 9.4 | 5.5 |
| Dry mouth | 5.6 | 6.4 | 5.5 | 6.0 | 6.5 |
| Constipation | 2.9 | 3.4 | 3.6 | 5.6 | 4.4 |
| Vomiting | 1.1 | 2.7 | 3.6 | 6.5 | 4.4 |
| Dyspepsia | 1.9 | 1.8 | 1.7 | 2.4 | 2.1 |
| Flatulence | 1.2 | 1.0 | 1.9 | 2.0 | 0.9 |
| Abdominal discomfort | 1.1 | 1.4 | 0.6 | 2.0 | 1.6 |
General Disorders and Administration Site Conditions Fatigue | 2.7 | 3.1 | 2.8 | 3.6 | 2.6 |
Infections and Infestations Nasopharyngitis | 3.9 | 5.3 | 4.0 | 3.6 | 4.9 |
Metabolism and Nutrition Disorders Decreased appetite | 1.0 | 2.1 | 0.7 | 0.7 | 1.6 |
Musculoskeletal and Connective Tissue Disorders Arthralgia | 0.9 | 0.9 | 0.9 | 1.8 | 1.1 |
| Nervous System | |||||
| Dizziness | 5.3 | 5.5 | 5.2 | 7.1 | 6.3 |
| Somnolence | 2.3 | 3.3 | 2.9 | 2.7 | 3.3 |
Table 2 Incidence of common adverse events* for Major Depressive Disorder, pool of 12 short-term studies | |||||
| Body System/Adverse Event | Percentage of Patients Reporting | ||||
Placebo (n = 1968) | Vortioxetine tablets 5 mg/day (n =1157) | Vortioxetine tablets 10 mg/day (n =1042) | Vortioxetine tablets 15 mg/day (n =449) | Vortioxetine tablets 20 mg/day (n =812) | |
| Sedation | 0.6 | 1.2 | 0.5 | 1.3 | 1.5 |
| Psychiatric Disorders | |||||
| Insomnia | 2.5 | 3.1 | 2.6 | 1.8 | 2.7 |
| Abnormal dreams | 0.8 | 0.4 | 0.5 | 1.6 | 1.4 |
| Skin and | |||||
| Subcutaneous Tissue | |||||
| Disorders | 1.7 | 2.3 | 2.3 | 1.8 | 0.7 |
| Hyperhidrosis | 0.4 | 0.4 | 1.3 | 1.6 | 1.8 |
| Pruritus generalised | |||||
| * Events included are those occurring in 1% or more of patients treated with vortioxetine tablets, and for which the incidence in patients treated with vortioxetine tablets was greater than the incidence in placebo- treated patients. | |||||
Male and Female Sexual Dysfunction
Changes in sexual desire, sexual performance and sexual satisfaction often occur as manifestations of psychiatric disorders, but they may also be a consequence of pharmacologic treatment.
The incidence of self-reported adverse sexual reactions was low and similar to placebo in clinical short- and long-term clinical studies with vortioxetine (5 to 20 mg/day). Table 3 shows the percentage of voluntarily reported adverse reactions related to sexual function in the short-term placebo-controlled studies in patients with MDD. Reported adverse events were classified using MedDRA, version 14.1.
Table 3 Incidence of sexual dysfunction adverse reactions in a pool of 12 placebo-controlled clinical trials For Major Depressive Disorder | ||
| Adverse Event | Percentage of Patients Reporting | |
Vortioxetine tablets (5-20 mg) (n =3460) | Placebo (n = 1968) | |
| Libido decreased | 0.7 | 0.6 |
| Orgasm abnormal | 0.3 | 0.2 |
| Anorgasmia | 0.2 | 0.0 |
| Loss of libido | 0.2 | 0.0 |
| Disturbance in sexual | ||
| arousal | <0.1 | 0.0 |
| Orgasmic sensation | ||
| decreased | <0.1 | <0.1 |
| Sexual dysfunction | <0.1 | <0.1 |
| In Males only1 | ||
| Ejaculation delayed | 0.5 | 0.1 |
| Erectile dysfunction | 0.3 | 0.4 |
| Ejaculation disorder | <0.1 | 0.0 |
| In Females only2 | ||
| Vulvovaginal dryness | <0.1 | 0 |
1 Denominator used was for males only (n=1153 for vortioxetine tablets; n=702 for Placebo). 2 Denominator used was for females only (n=2307 for vortioxetine tablets; n=1266 for Placebo). | ||
Because voluntarily reported adverse sexual reactions are presumed to be underreported, in part because patients and physicians may be reluctant to discuss them, the Arizona Sexual Experiences Scale (ASEX), a validated measure designed to identify sexual side effects, was used prospectively in 7 short-term placebo-controlled studies; 6 studies in patients with MDD and 1 study in patients with Generalized Anxiety Disorder.
The ASEX scale includes five questions that pertain to the following aspects of sexual function: 1) sex drive, 2) ease of arousal, 3) ability to achieve erection (men) or lubrication (women), 4) ease of reaching orgasm, and 5) orgasm satisfaction. Each item is rated from 1 to 6, with higher scores indicating greater dysfunction. Sexual dysfunction was defined as a subject scoring any of the following on the ASEX scale at two consecutive visits during the study: 1) total score ≥19; 2) any single item ≥5; 3) three or more items each with a score ≥4. For patients without sexual dysfunction at baseline, the incidence of treatment-emergent sexual dysfunction on the ASEX is show in Table 4 below. Vortioxetine tablets was associated with higher incidences of treatment- emergent sexual dysfunction compared to placebo, when evaluated by the ASEX scale. Physicians should routinely inquire about possible sexual side effects during treatment with APO-VORTIOXETINE.
Table 4 Incidence (n/N)* of treatment-emergent sexual dysfunction based on ASEX in a pool of 7 placebo-controlled clinical trials | |||||
Vortioxetine tablets (5 mg) | Vortioxetine tablets (10 mg) | Vortioxetine tablets (15 mg) | Vortioxetine tablets (20 mg) | Placebo | |
| Females | N=65 22% | N=94 23% | N=57 33% | N=67 34% | N=135 20% |
| Males | N=67 16% | N=86 20% | N=67 19% | N=59 29% | N=162 14% |
*incidence based on n=number of subjects with treatment-emergent ASEX sexual dysfunction at 2 consecutive visits/ N=number of subjects without sexual dysfunction at baseline.
Discontinuation Symptoms
Discontinuation symptoms were evaluated in 7 placebo-controlled trials (6 short-term and 1 long-term) during a two-week period following abrupt discontinuation of vortioxetine tablets. In 4 of the short-term studies (8-weeks), the Discontinuation-Emergent Signs and Symptoms (DESS) Checklist was also used. Abrupt discontinuation of vortioxetine was associated with increased frequency of discontinuation-emergent adverse events and in the frequency of signs and symptoms in the DESS checklist, as compared to placebo. The most common symptoms associated with discontinuation were headache, increased dreaming/nightmares, mood swings, muscle tension/stiffness, sudden outbursts of anger, dizziness/vertigo and nose running. Patients should be monitored for discontinuation symptoms when discontinuing treatment with APO-VORTIOXETINE.
When discontinuing APO-VORTIOXETINE, a gradual reduction in the dose, rather than an abrupt cessation, is recommended whenever possible (see 4.2.1 Discontinuing Treatment).
Weight Changes
Vortioxetine tablets had no clinically meaningful effect on body weight as measured by the mean change from baseline in the long-term (24 to 64 weeks) and short-term (6 to 8 weeks) placebo- controlled studies. The mean changes in weight in a long-term placebo-controlled study in patients with MDD was +0.4 kg in the vortioxetine tablets 5 or 10 mg/day group and +0.1 kg in placebo group. The proportions of patients with a weight gain ≥7% were 6.5 % in the vortioxetine tablets 5 or 10 mg/day group and 5.8% in the placebo group. The proportions of patients with a weight decrease ≥7% were 3.5% in the vortioxetine tablets 5 or 10 mg/day group and 2.6% in the placebo group.
Cardiovascular Parameters
Vortioxetine tablets and placebo groups in MDD patients were compared with respect to mean change from baseline in vital signs (pulse, systolic blood pressure, and diastolic blood pressure)
and the incidence of patients meeting criteria for potentially clinically significant changes from baseline in these variables. The analyses did not reveal any clinically important changes in blood pressure or heart rate associated with vortioxetine tablets treatment.
In a randomized, placebo- and positive-controlled, parallel group, thorough QTc study in 340 healthy subjects, changes in maximum mean systolic blood pressure of 2.8 mmHg (90% CI 0.7, 4.8) for vortioxetine tablets 10 mg/day and 4.8 mmHg (90% CI 2.7, 7.0) for vortioxetine tablets 40 mg/day were observed after 14 days treatment (see 10.3 Pharmacokinetics, Special Populations and Conditions, Electrocardiography and Hemodynamics).
In the pooled short-term studies in MDD, the mean change in systolic blood pressure from baseline to last assessment was -0.35 mmHg for all vortioxetine doses combined and -
1.0 mmHg for placebo. For vortioxetine 20 mg alone the mean change was +0.35 mmHg. In a study in elderly patients with MDD, the mean change in systolic blood pressure from baseline to last assessment was -1.1 mmHg for vortioxetine and -3.9 mmHg for placebo. Vortioxetine was not associated with increased incidence of individual potentially clinically significant (PCS) changes in blood pressure in the short-term MDD studies.
Electrocardiograms
Vortioxetine tablets have not been associated with any clinically significant effect on ECG parameters, including QT, QTc, PR and QRS intervals, or with any arrhythmogenic potential in clinical studies. In a randomized, placebo- and positive-controlled, parallel group, thorough QTc study in 340 healthy subjects, treatment with vortioxetine tablets 10 or 40 mg/day for 14 days did not prolong QT/QTc intervals, and there was no plasma concentration-QTc relationship observed.
In the thorough QTc study in healthy subjects, treatment with vortioxetine tablets 10 or 40 mg/day for 14 days was associated with modest decreases in heart rate of -4.7 bpm (90% CI -6.8, -2.7) for 10 mg/day and -5.4 bpm (90% CI -7.4, -3.4) for 40 mg/day after 14 days treatment (see 10.3 Pharmacokinetics, Special Populations and Conditions, Electrocardiography and Hemodynamics).
In the pooled short-term studies in MDD, the mean change in ECG heart rate from baseline to last assessment was -0.06 bpm for all vortioxetine doses combined and +0.9 bpm for placebo. For the individual vortioxetine doses the mean changes were -0.02 (5 mg), -0.4 (10 mg), -0.24 (15 mg), and +0.38 (20 mg). In a study in elderly patients with MDD, the mean change in ECG heart rate from baseline to last assessment was -1.55 bpm for vortioxetine and -0.23 bpm for placebo. Vortioxetine was not associated with increased incidence of individual potentially clinically significant (PCS) changes in ECG heart rate in the short-term MDD studies.
Adverse Events During Treatment up to 64 weeks in MDD
The adverse event profile of vortioxetine tablets in a long-term study in patients with MDD was similar to that observed in short-term studies.
Patients who were remitters following 12 weeks of acute, open-label treatment with vortioxetine tablets were observed for relapse during a double-blind, placebo-controlled treatment period (see 14.1 Clinical Trials by Indication). Because the double- blind period was planned to end simultaneously for all patients, the planned duration of treatment ranged from a minimum of 24 weeks to up to 64 weeks, depending on the time of enrollment. During the long-term, double-blind treatment period the overall incidence of Treatment-Emergent Adverse Events (TEAEs) was 62% for vortioxetine tablets and 64% for placebo. Table 5 enumerates the incidence of TEAEs that occurred in 204 depressed patients who received vortioxetine tablets at 5 or 10 mg/day for up to 24 to 64 weeks. Events included are those occurring in 2% or more of patients treated with vortioxetine tablets, and for which the incidence in patients treated with vortioxetine tablets was greater than the incidence in placebo-treated patients. Reported adverse events were classified using MedDRA, version 12.0.
Table 5 Incidence of adverse events ≥2%1 in remitted patients with MDD receiving double-blind treatment for up to 24 to 64 weeks2 | ||
| Adverse Event | Percentage of Patients Reporting | |
Vortioxetine tablets 5 or 10 mg (n = 204) | Placebo (n = 192) | |
| Nausea | 8.8 | 3.1 |
| Gastroenteritis | 5.4 | 3.1 |
| Abdominal pain upper | 4.9 | 1.0 |
| Insomnia | 2.5 | 1.6 |
| Dry mouth | 2.0 | 0.0 |
| Cough | 2.0 | 0.5 |
| Asthenia | 2.0 | 0.5 |
| Influenza-like illness | 2.0 | 1.0 |
| Myalgia | 2.0 | 0.5 |
| Urinary tract infection | 2.0 | 0.5 |
1Events included are those occurring in 2% or more of patients treated with vortioxetine tablets (5 or 10 mg/day), and for which the incidence was greater than the incidence in placebo-treated patients. 2Median duration of the double-blind treatment was 27 weeks for placebo and 28 weeks for vortioxetine tablets (5 or 10 mg/day). | ||
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Clinical Trial Adverse Events in Pediatric patients with depressive or anxiety disorder:
A total of 304 children aged 7 to 11 years and 308 adolescents aged 12 to 17 years with major depressive disorder (MDD) were treated with vortioxetine in two double-blind, placebo-controlled studies, respectively. In general, the adverse event profile of vortioxetine in children and adolescents was similar to that seen for adults, except for higher incidences of headache, vomiting, abdominal pain-related events. In adolescents specifically, higher reports of suicidal ideation and self-harm were reported in vortioxetine treated patients in comparison to those that received placebo. The most commonly reported adverse events in the vortioxetine treatment groups in both studies were nausea, headache and vomiting.
The pharmacokinetics, safety and tolerability of vortioxetine 5 to 20 mg per day was assessed in 48 pediatric patients (ages 7 to 17 years) with a diagnosis of depressive or anxiety disorder in an open-label trial, which consisted of a main study period of 14 days and a 6-month extension period. Adverse events reported with an incidence of ≥10% during the main or during the extension study period were headache, nausea, sedation, abdominal pain upper, fatigue, vomiting and dysmenorrhoea. APO-VORTIOXETINE is not indicated for use in patients below the age of 18. The efficacy and safety of vortioxetine tablets have not been established in patients below 18 years of age (see also 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
8.3 Less Common Clinical Trial Adverse Reactions
The events listed below present treatment emergent adverse events occurring in less than 1% of the patients treated with vortioxetine tablets (5 to 20 mg/day) in 12 short-term placebo-controlled studies in depressed patients. The listing does not include events: 1) already listed in previous tables or elsewhere in labelling, 2) for which a drug cause was remote, 3) which were so general as to be uninformative, 4) which were not considered to have significant clinical implications, or 5) which occurred at a rate equal to or less than placebo.
The reported adverse events were classified using MedDRA, version 14.1. The events are categorized by body system according to the following definitions: frequent adverse reactions are those occurring in at least 1/100 patients; infrequent adverse reactions are those occurring in 1/100 to 1/1,000 patients; rare reactions are those occurring in less than 1/1,000 patients.
Blood and Lymphatic System Disorders
Rare: Leukopenia
Cardiac Disorders
Infrequent: Sinus bradycardia, angina pectoris
Rare: Ventricular extrasystoles
Ear and Labyrinth Disorders
Infrequent: Vertigo
Eye Disorders
Infrequent: Dry eye, visual impairment
Rare: Visual acuity reduced, vitreous floaters, eye pain, mydriasis (which may lead to acute narrow angle glaucoma)
Gastrointestinal Disorders
Infrequent: Abdominal distension, gastritis, epigastric discomfort, salivary hypersecretion
Rare: Aphthous stomatitis, eructation, glossitis, bowel movement irregularity, cheilitis, colitis, haematochezia
General Disorders and Administration Site Conditions
Infrequent: Chest discomfort, malaise, non-cardiac chest pain
Hepatobiliary Disorders
Rare: Hepatic function abnormal
Immune System Disorders
Rare: Hypersensitivity
Investigations
Infrequent: Weight increased, electrocardiogram QT prolonged, heart rate increased, low density lipoprotein increased, blood cholesterol increased, blood triglycerides increased, blood creatine phosphokinase increased, blood gamma-glutamyl transferase increased
Rare: Blood alkaline phosphatase increased, hepatic enzyme increased, transaminases increased
Metabolism and Nutrition Disorders
Infrequent: Dehydration
Rare: Hyperglycaemia, dyslipidaemia, glucose tolerance impaired, hypoglycaemia
Nervous System
Infrequent: Dysgeusia, lethargy, tremor, myoclonus, hypersomnia, restless legs syndrome, memory impairment
Rare: Ageusia, psychomotor hyperactivity, convulsion, hyperreflexia, muscle contractions involuntary, sensory disturbance, formication
Psychiatric Disorders
Infrequent: Tension, bruxism, restlessness, derealisation, depersonalization
Rare: Suicide attempt, terminal insomnia, euphoric mood
Renal and Urinary Disorders Infrequent: Micturition urgency, nocturia Rare: Urine odour abnormal
Reproductive System and Breast Disorders
Infrequent: Menstruation delayed, polymenorrhoea, breast tenderness
Respiratory, Thoracic and Mediastinal Disorders
Infrequent: Yawning
Rare: Respiratory tract congestion, dry throat
Skin and Subcutaneous Tissue Disorders
Infrequent: Pruritus, night sweats, rash, urticaria
Rare: Dermatitis allergic, psoriasis, rash erythematous, skin irritation
Vascular Disorders
Infrequent: Hypertension, flushing
Rare: Hypotension
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Not Applicable.
8.5 Post-Market Adverse Reactions
The following adverse events have been identified during post-approval use of vortioxetine tablets. These events are reported voluntarily from a population of uncertain size, and it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Endocrine disorders
Hyperprolactinaemia
Gastrointestinal system
Acute pancreatitis
Immune system disorders
Anaphylactic reaction
Nervous system disorders
Serotonin toxicity, headache
Psychiatric disorders
Agitation, aggression
Skin and subcutaneous tissue disorders
Angioedema
Vascular disorders
Haemorrhage (including contusion, ecchymosis, epistaxis, gastrointestinal or vaginal haemorrhage)
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions Monoamine Oxidase Inhibitors (MAOIs) (see 2 CONTRAINDICATIONS and 9.2 Drug Interactions Overview) |
|---|
9.2 Drug Interactions Overview
Vortioxetine is extensively metabolized, primarily through oxidation and subsequent glucuronic acid conjugation. In vitro, the cytochrome P450 isozymes CYP2D6, CYP3A4/5, CYP2C19, CYP2C9, CYP2A6, CYP2C8 and CYP2B6 are involved in the metabolism of vortioxetine.
Drugs metabolized by CYP2D6
CYP2D6 is the primary enzyme catalyzing the metabolism of vortioxetine to its major, pharmacologically inactive, carboxylic acid metabolite. Caution is recommended when APO-VORTIOXETINE is co-administered with drugs that are mainly metabolized by CYP2D6, particularly those that have a narrow therapeutic index (see 10.3 Pharmacokinetics, Metabolism).
Drugs with high protein binding
Vortioxetine was highly bound to plasma protein in vitro (>99%) therefore administration of APO-VORTIOXETINE to a patient taking another drug that is highly protein bound may cause increased free concentrations of the other drug, potentially resulting in adverse events. Conversely, adverse effects may result from displacement of protein bound vortioxetine by other tightly bound drugs.
Monoamine Oxidase Inhibitors (MAOIs)
Combined use of APO-VORTIOXETINE and MAOIs is contraindicated due to the potential for serious reactions with features resembling serotonin toxicity or neuroleptic malignant syndrome (see 2 CONTRAINDICATIONS; 7 WARNINGS AND PRECAUTIONS, Neurologic Serotonin Toxicity /Neuroleptic Malignant Syndrome). In patients receiving SSRIs in combination with a MAOI, there have been reports of serious, sometimes fatal, reactions including hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes, including extreme agitation progressing to delirium and coma. These reactions have also been reported in patients who have recently discontinued SSRI treatment and have been started on a MAOI. Some cases presented with features resembling serotonin toxicity or neuroleptic malignant syndrome. APO-VORTIOXETINE should not be used in combination with a MAOI, (including linezolid, an antibiotic which is a reversible non-selective MAOI, and methylene blue, which is a MAOI) or within 14 days of discontinuing treatment with a MAOI. Similarly, at least 21 days should elapse after discontinuing APO-VORTIOXETINE treatment before starting a MAOI (see 2 CONTRAINDICATIONS).
Serotonergic Medicinal Products
Based on the mechanism of action of vortioxetine tablets and the potential for serotonin syndrome, caution is advised when APO-VORTIOXETINE is co-administered with other drugs or agents that may affect the serotonergic neurotransmitter systems, such as tryptophan, triptans, serotonin reuptake inhibitors, lithium, St. John's Wort, dextromethorphan, and opioids (including tramadol, fentanyl and its analogues, tapentadol, meperidine, methadone and pentazocine) (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Toxicity /Neuroleptic Malignant Syndrome). Concomitant use of APO-VORTIOXETINE and MAOIs (including linezolid and methylene blue), is contraindicated (see 2 CONTRAINDICATIONS).
Triptans (5HT1 agonists)
Cases of life-threatening serotonin toxicity have been reported during combined use of SSRIs/SNRIs and triptans. If concomitant treatment with APO-VORTIOXETINE and a triptan is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Toxicity /Neuroleptic Malignant Syndrome).
Drugs Affecting Platelet Function (e.g. NSAIDs, ASA and other anticoagulants)
Serotonin release by platelets plays an important role in hemostasis. Epidemiological studies of the case-control and cohort design that have demonstrated an association between use of psychotropic drugs that interfere with serotonin reuptake and the occurrence of upper gastrointestinal bleeding have also shown that concurrent use of an NSAID, ASA or other anticoagulants may potentiate the risk of bleeding.
Altered anticoagulant effects, including increased bleeding, have been reported when SSRIs and SNRIs are co-administered with warfarin. Patients receiving warfarin therapy should be carefully monitored when APO-VORTIOXETINE is initiated or discontinued. (See 7 WARNINGS AND PRECAUTIONS, Hematologic, Abnormal Bleeding).
Medicinal Products Lowering the Seizure Threshold
Antidepressants with serotonergic effect can lower the seizure threshold. Caution is advised when concomitantly using other medicinal products capable of lowering the seizure threshold (e.g. antidepressants (tricyclics, SSRIs, SNRIs), neuroleptics (phenothiazines, thioxanthenes and butyrophenones), mefloquin, bupropion and tramadol) (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Seizures).
Lithium and tryptophan
There have been reports of enhanced effects when antidepressants with serotonergic effect have been given together with lithium or tryptophan, therefore concomitant use of vortioxetine with these medicinal products should be undertaken with caution.
Alcohol
No effect on the pharmacokinetics of vortioxetine or ethanol and no significant impairment, relative to placebo, in cognitive function was observed when vortioxetine in a single dose of
20 mg or 40 mg was co-administered with a single dose of 0.6 g/kg ethanol in healthy subjects. However, alcohol intake is not advisable during antidepressant treatment.
Other CNS-Active Drugs
The risk of using vortioxetine tablets in combination with other CNS-active drugs has not been systematically evaluated. Consequently, caution is advised if the concomitant administration of APO-VORTIOXETINE and such drugs is required.
9.3 Drug-Behavioural Interaction
This information is not available for this drug product
9.4 Drug-Drug Interactions
The drugs listed in Table 6 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 6 Drug-Drug Interactions | |||
| Source of Evidence | Effect | Clinical comment | |
| Bupropion | CT | The exposure of vortioxetine increased 2.3-fold for AUC when vortioxetine 10 mg/day was co-administered with bupropion (a strong CYP2D6 inhibitor 150 mg twice daily) for 14 days in healthy subjects. Co-administration resulted in a higher incidence of adverse events when bupropion was added to vortioxetine than when vortioxetine was added to bupropion. | Reduce the dose of vortioxetine by half if strong CYP2D6 inhibitors (e.g. bupropion, cinacalcet, quinidine, fluoxetine, paroxetine) are co-administered (see 4.2 Recommended Dose and Dosage Adjustment, Cytochrome P450 Inhibitors). |
Table 6 Drug-Drug Interactions | |||
| Source of Evidence | Effect | Clinical comment | |
| CYP2D6 Poor Metabolizers | T | Co-administration of strong inhibitors of CYP3A4 (such as itraconazole, voriconazole, clarithromycin, telitromycin, nefazodone and many of the HIV protease inhibitors) and inhibitors of CYP2C9 (such as fluconazole and amiodarone) to CYP2D6 poor metabolizers has not been investigated specifically. | It is anticipated that such co-administration will lead to increased exposure of vortioxetine in these patients and vortioxetine dosage adjustment may be required (see 10.3 Pharmacokinetics, Special Populations and Conditions, Genetic Polymorphism (CYP2D6 Poor Metabolizers)). |
| Rifampicin | CT | When a single dose of 20 mg vortioxetine was co-administered following 10 days of rifampicin 600 mg/day (an inducer of CYP isozymes) in healthy subjects, a 72% decrease in AUC of vortioxetine was observed. | Depending on individual patient response, a vortioxetine dose adjustment may be considered if a broad cytochrome P450 inducer (e.g. rifampicin, carbamazepine, phenytoin) is added to vortioxetine treatment (see 4.2 Recommended Dose and Dosage Adjustment, Cytochrome P450 Inducers). |
| Lithium | CT | No clinically relevant effect was observed during steady-state lithium exposure following co-administration with vortioxetine 10 mg/day for 14 days in healthy subjects. | Concomitant use of vortioxetine with lithium should be undertaken with caution (see 9.2 DRUG INTERACTIONS, Drug Interactions Overview). |
Table 6 Drug-Drug Interactions | |||
| Source of Evidence | Effect | Clinical comment | |
| Ketoconazole and Fluconazole | CT | When a single dose of vortioxetine was co- administered following 6 days of ketoconazole 400 mg/day (a CYP3A4/5 and P-glycoprotein inhibitor) or following 6 days of fluconazole 200 mg/day (a CYP2C9, CYP2C19 and CYP3A4/5 inhibitor) in healthy subjects, a 1.3-fold and 1.5- fold increase, respectively in vortioxetine AUC was observed. | No vortioxetine dose adjustment is needed. |
| Omeprazole | CT | No inhibitory effect of 40 mg single-dose omeprazole (CYP2C19 inhibitor) was observed on the multiple-dose pharmacokinetics of vortioxetine in healthy subjects. | No vortioxetine dose adjustment is needed. |
| Substrates of CYP2C19 (omeprazole, diazepam), CYP3A4/5 (ethinyl estradiol, midazolam), CYP2B6 (bupropion), CYP2C9 (tolbutamide, S- warfarin), CYP1A2 (caffeine) or CYP2D6 (dextromethorphan) | CT | Multiple doses of vortioxetine in healthy subjects had no clinically significant effects on plasma concentrations of known substrates of CYP2C19 (omeprazole, diazepam), CYP3A4/5 (ethinyl estradiol, midazolam), CYP2B6 (bupropion), CYP2C9 (tolbutamide, S-warfarin), CYP1A2 (caffeine) or CYP2D6 (dextromethorphan). | No dose adjustment of these substrates is needed. |
Table 6 Drug-Drug Interactions | |||
| Source of Evidence | Effect | Clinical comment | |
| Diazepam | CT | No significant pharmacodynamic interactions or cognitive impairments were observed following co- administration of vortioxetine with a single 10 mg dose of diazepam. | No vortioxetine dose adjustment is needed. |
| Oral contraceptive | CT | No significant effects, relative to placebo, were observed in the levels of sex hormones following co-administration of vortioxetine with a combined oral contraceptive (ethinyl estradiol 30 mcg/ levonorgestrel 150 mcg) for 21 days. | No vortioxetine dose adjustment is needed. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
No effect from food on the pharmacokinetics of vortioxetine was observed (see 10.3 Pharmacokinetics, Absorption).
9.6 Drug-Herb Interactions
St. John’s Wort
Concomitant use of antidepressants with serotonergic effect and herbal remedies containing St. John´s Wort (Hypericum perforatum) may result in an increased incidence of adverse reactions including serotonin toxicity (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Toxicity/Neuroleptic Malignant Syndrome).
9.7 Drug-Laboratory Test Interactions
Interference with urine drug screen
There have been reports of false positive results in urine enzyme immunoassays for methadone in patients who have taken vortioxetine. Caution should be exercised in the interpretation of positive urine drug screen results, and confirmation by an alternative analytical technique (e.g., chromatographic methods) should be considered.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The antidepressant effect of vortioxetine is thought to be related to modulation of serotonergic neurotransmission in the CNS through mechanisms that include inhibition of reuptake of serotonin (5-HT) at the 5-HT transporter (5-HTT) and activity at several human 5-HT receptors, including 5-HT1A receptor agonism, 5-HT1B receptor partial agonism, and 5-HT3, 5-HT1D and 5- HT7 receptor antagonism. The precise contribution of the individual targets to the net effect of vortioxetine and the exact mechanism of action is not fully understood.
10.2 Pharmacodynamics
In vitro, vortioxetine binds with high affinity to the human 5-HT transporter (5-HTT) (Ki = 1.6 nM) and inhibits reuptake of serotonin (IC50 = 5.4 nM). Lower affinity binding was observed at the human norepinephrine (Ki = 113 nM) and human dopamine (Ki > 1000 nM) transporters.
Vortioxetine binds in vitro to the human 5-HT3 (Ki = 3.7 nM), 5-HT1A (Ki = 15 nM), 5-HT7 (Ki = 18 nM), 5-HT1B (Ki = 33 nM) and 5-HT1D (Ki = 54 nM) receptors. Vortioxetine has antagonist activity at the human 5-HT3, 5-HT1D and 5-HT7 receptors (cIC50 = 3.5 nM, 25 nM, and 450 nM respectively), partial agonist activity at the human 5-HT1B receptor (EC50 = 120 to 460 nM), and agonist activity at the human 5-HT1A receptor (EC50 = 199 nM). The role of these activities in the antidepressant effect of vortioxetine has not been established.
In humans, two positron emission tomography (PET) studies using 5-HT transporter ligands (11C-MADAM or 11C-DASB) to quantify the 5-HT transporter occupancy in the brain across different dose levels indicated that mean 5-HT transporter occupancy was approximately 50% at 5 mg/day, 65% at 10 mg/day and approximately 80% at 20 mg/day in the specific regions of interest.
10.3 Pharmacokinetics
The pharmacological activity of vortioxetine is due to the parent drug. The pharmacokinetics are linear and time-independent in the dose range studied (2.5 to 60 mg/day). Steady state plasma levels are achieved in approximately 2 weeks.
Table 7 Summary of Vortioxetine Tablets Pharmacokinetic Parameters in Young Healthy Adult Male Subjects | ||||||
| Mean | Cmax (ng/mL) | tmax (h) | AUC0-inf (ng.h/mL) | AUC0-24h (ng.h/mL) | Clearance (L/h) | Volume of distribution (L) |
| Single dose | ||||||
10 mg (N=6) | 2.70 | 8.00 | 282 | N/A | 50.67a | 3697 |
20 mg (N=6) | 5.69 | 8.00 | 349 | N/A | 62.42 | 3871 |
| Multiple dose | ||||||
20 mg (N=6) | 19.21 | 7.00 | N/A | 361 | 61.85 | 4340 |
a N = 5 for Clearance; N/A= not applicable
Following single doses of vortioxetine to young adult women and elderly men and women, the pharmacokinetic parameters of vortioxetine were generally consistent with the values observed in young adult men (Table 7). Following multiple doses of vortioxetine, there was an increase in the exposure of vortioxetine in healthy elderly subjects compared to young healthy adult subjects. Cmax, AUC0-24h, and elimination half-life (t1/2) were increased and oral clearance was decreased in elderly subjects compared to young adult subjects (see 7.1.4 Geriatrics; 4.2 Recommended Dose and Dosage Adjustment, Geriatrics; and 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
Absorption: Vortioxetine is slowly but well absorbed after oral administration and the peak plasma concentration is reached within 7 to 11 hours. Following multiple dosing of 5, 10, and 20 mg/day, mean Cmax values of 9 to 33 ng/mL were observed. The absolute bioavailability is 75%. No effect of food on the pharmacokinetics was observed.
Distribution: The mean volume of distribution (Vss) is 2,600 L, indicating extensive extravascular distribution. Vortioxetine is highly bound to plasma proteins (98 to 99%) and the binding appears to be independent of vortioxetine plasma concentrations.
Metabolism: Vortioxetine is extensively metabolized, primarily through oxidation and subsequent glucuronic acid conjugation.
In vitro, the cytochrome P450 isozymes CYP2D6, CYP3A4/5, CYP2C19, CYP2C9, CYP2A6, CYP2C8 and CYP2B6 are involved in the metabolism of vortioxetine. CYP2D6 is the primary enzyme catalyzing the metabolism of vortioxetine to its major, pharmacologically inactive, carboxylic acid metabolite.
Vortioxetine did not inhibit CYP isozymes CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP2E1, or CYP3A4/5 in vitro. Vortioxetine did not induce CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, and CYP3A4/5 in an in vitro study in cultured human hepatocytes. In vitro vortioxetine is not a substrate or inhibitor of the P-gp transporter (see 9 DRUG INTERACTIONS).
Elimination: The mean elimination half-life and oral clearance are 66 hours and 33 L/h, respectively. Approximately 2/3 of the inactive vortioxetine metabolites are excreted in the urine and approximately 1/3 in the faeces. Only negligible amounts of unchanged vortioxetine are excreted in the urine.
Special Populations and Conditions
- Pediatrics: APO-VORTIOXETINE is not indicated for use in patients below the age of 18 (see 1.1 Pediatrics; 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
Pharmacokinetics of vortioxetine in paediatric patients with major depressive disorder following oral administration of 5 to 20 mg once daily was characterized using population modelling analyses based on data from a pharmacokinetic study (7 to 17 years) and two efficacy and safety studies (7 to 17 years). The pharmacokinetics of vortioxetine in pediatric patients were similar to that observed in adult patients.
- Geriatrics: In elderly healthy subjects (≥65 years; n=20), the exposure of vortioxetine increased up to 27% (Cmax and AUC) compared to young healthy adult control subjects (≤45 years) after multiple doses of 10 mg/day. A higher frequency of gastrointestinal adverse events was reported in elderly subjects compared to young adult subjects (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
- Sex: Systemic exposures between males and females are similar and no dose adjustment is needed.
- Genetic Polymorphism (CYP2D6 Poor Metabolizers): The plasma concentration of vortioxetine was approximately two times higher in CYP2D6 poor metabolizers than in extensive metabolizers. In the presence of strong CYP3A4/2C9-inhibitors, the exposure could potentially be higher and a dosage adjustment may be required (see 9.4 Drug-Drug Interactions).
- Ethnic origin: No dose adjustment on the basis of race or ethnicity is needed. Race or ethnicity had no apparent effect on the pharmacokinetics of vortioxetine.
Hepatic Insufficiency: The pharmacokinetics in subjects (N = 6 to 8) with mild, moderate, or severe hepatic impairment (Child-Pugh Criteria A, B, or C, respectively) were compared to healthy volunteers. After doses of 10 mg (mild and moderate) or 5 mg (severe), the changes in AUC were less than 10% in subjects with mild or moderate hepatic impairment, and 44% higher in those with severe hepatic impairment while the
- max was 24% lower. No dose adjustment is needed on the basis of hepatic function, however, caution should be exercised (see 4.2 Recommended Dose and Dosage Adjustment and 7 WARNINGS AND PRECAUTIONS).
Renal Insufficiency: Following a single dose of 10 mg vortioxetine, renal impairment estimated using the Cockcroft-Gault formula (mild, moderate, and severe; n=8 per group) caused modest exposure increases (up to 30%), compared to healthy matched controls.
No dose adjustment is needed on the basis of renal function, however, caution should be exercised (see 4.2 Recommended Dose and Dosage Adjustment and 7 WARNINGS AND PRECAUTIONS).
Electrocardiography and Haemodynamics:
Vortioxetine was assessed for effects on ECG parameters and blood pressure in a randomised, double-blind, placebo- and positive-controlled, 4-arm parallel group study performed in healthy male volunteers (N=82/treatment arm). Vortioxetine was tested at a therapeutic dose of 10 mg per day for 14 days and a supratherapeutic dose of 40 mg per day for 14 days. ECG data were assessed at 0 h, and 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 12, 16 and 23.5 h post-dose on day 14.
At the therapeutic dose of 10 mg per day, the maximum mean difference from placebo using QTcFm (QTcFm = QT+ 0.154[1- RR]) was 4.0 ms (90% CI 1.3, 6.7) at 4 h. At the dose of 40 mg per day, the maximum mean difference from placebo using QTcFm was 4.6 ms (90% CI 2.2, 7.1) at 4 h. No noteworthy effects on the PR interval or QRS duration were observed in this study.
Vortioxetine was observed to have a modest negative chronotropic effect. The maximum mean decrease observed in heart rate was of -4.7 bpm (90% CI -6.8, -2.7) for 10 mg per day and -5.4 bpm (90% CI -7.4, -3.4) for 40 mg per day on Day 14.
Supine systolic blood pressure was increased by vortioxetine. The maximum mean increase observed in systolic blood pressure was of 2.8 mmHg (90% CI 0.7, 4.8) for 10 mg per day and 4.8 mmHg (90% CI 2.7, 7.0) for 40 mg per day on Day 14. No noteworthy effects on diastolic blood pressure were observed in this study.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature 15°C to 30°C. Protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
Not Applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Vortioxetine hydrobromide
Chemical name: 1-[2-(2,4-Dimethyl-phenylsulfanyl)-phenyl]-piperazine hydrobromide Molecular formula and molecular mass: C18H22N2S, HBr (379.36 g/mol)
Structural formula:
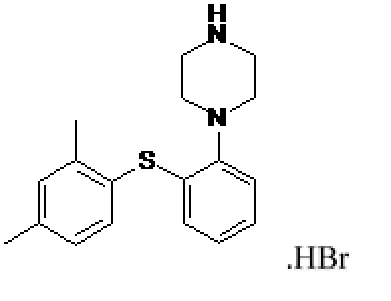
Physicochemical properties: The drug substance is a white to off-white. Soluble in methanol, dimethyl formamide, dimethyl sulfoxide and ethanol, pH being 5.05 (1% w/v aqueous suspension).
Melting point: = 231°C
pKa = 9.20 and 3.10
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Major Depressive Disorder
Short-term studies
More than 3,000 patients were treated with vortioxetine tablets in short-term MDD studies (of up to 8 weeks duration) as listed in Table 8.
The efficacy of vortioxetine tablets 5 mg, 10 mg, 15 mg, and 20 mg once daily in the treatment of MDD was evaluated in ten short-term, randomized, double-blind, placebo-controlled studies in adults, and one short-term placebo-controlled study in elderly patients. All studies included male and female inpatients and outpatients, who met the Diagnostic and Statistical Manual of Mental Disorders (DSM-IV-TR) criteria for MDD. The studies in adults included patients 18 to 75 years old (mean age range 43 to 47 years) with baseline total scores on the Montgomery Asberg Depression Rating Scale (MADRS) > 26 in seven studies, > 30 in two studies and > 22 in one study. The study of elderly patients included patients who were 65 years of age or older (range 64 to 88 years), with at least one previous major depressive episode before 60 years of age, a baseline MADRS total score > 26 and no comorbid cognitive impairment (Mini Mental State Examination score > 24 at screening). Approximately two-thirds of the patients included in the short-term studies were female.
All short-term studies were of similar design. Patients received fixed doses of vortioxetine tablets 5 mg, 10 mg, 15 mg or 20 mg once daily for 6 or 8 weeks (two 6-week studies, nine 8-week studies). Six of the studies, including the study in elderly patients, included an active reference (SNRI) comparator arm. The primary outcome measure was the mean change from baseline to Week 6/Week 8 in the MADRS total score (seven studies) or the 24-item Hamilton Rating Scale for Depression (HAM-D24) (four studies). Five of the studies in adults were conducted in countries outside the United States (non-US) and five were conducted only in the United States (US). The study in elderly patients included patients from non-US countries and from the US.
Study Results
The efficacy of vortioxetine tablets 5 mg, 10 mg, 15 mg, and 20 mg once daily was demonstrated in at least one randomized, double-blind, placebo-controlled, 6/8-week, fixed-dose study (including the study in the elderly), as measured by improvement in the primary outcome measure (change from baseline to Week 6/8 in MADRS or HAM-D24 total score). In the non-US studies efficacy was demonstrated with vortioxetine tablets 5 mg and 10 mg in two studies and with 15 mg and 20 mg in one study. Efficacy was demonstrated with vortioxetine tablets 20 mg in two US studies. In the elderly study, which included US and non-US patients (majority non-US), efficacy was demonstrated with vortioxetine tablets 5 mg (Table 8). Less than 100 elderly patients included in the short-term studies in adults received vortioxetine tablets at doses above 5 mg/day.
In the studies demonstrating significant improvement on the primary endpoint, vortioxetine tablets also showed significant improvement over placebo on key secondary efficacy measures including the proportions of responders (defined as > 50% decrease from baseline in MADRS total score at Week 6/8), proportions of remitters (defined as MADRS total score < 10 at Week 6/8, and in the Clinical Global Impression-Improvement (CGI-I) score at Week 8.
Table 8 - Change from baseline to Week 6/8 in MADRS or HAM-D24 total score in short- term
MDD clinical trials
Study number [Primary Measure] | Treatment group | Number of patients | Mean baseline score (SD) | LS Mean change from baseline (SE) | LS Mean difference from placebo (95% CI) | p-value | |||||
Study 1*a,c [MADRS] Non-US | vortioxetine tablets 5 mg | 108 | 34.1 (2.6) | -20.4 (1.0) | -5.9 (-8.6, -3.2) | <0.0001 | |||||
| vortioxetine tablets 10 mg | 100 | 34.0 (2.8) | -20.2 (1.0) | -5.7 (-8.5, -2.9) | <0.0001 | ||||||
| Placebo | 105 | 33.9 (2.7) | -14.5 (1.0) | ||||||||
Study 2*b, c [MADRS] Non-US | vortioxetine tablets 5 mg vortioxetine tablets 10 mg Placebo | 155 151 145 | 32.7 (4.8) 31.8 (3.9) 31.7 (4.3) | -16.5 (0.8) -16.3 (0.8) -14.8 (0.8) | -1.7 (-3.9, 0.5) -1.5 (-3.7, 0.7) | NS | |||||
Study 3b, d [HAM-D24] Non-US | vortioxetine tablets 5 mg vortioxetine tablets 10 mg Placebo | 139 139 139 | 32.2 (5.0) 33.1 (4.8) 32.7 (4.4) | -15.4 (0.7) -16.2 (0.8) -11.3 (0.7) | -4.12 (-6.2, -2.1) -4.9 (-7.0, -2.9) | <0.001 <0.001 | |||||
Study 4*b, d [MADRS] Non-US | vortioxetine tablets 15 mg vortioxetine tablets 20 mg Placebo | 149 151 158 | 31.8 (3.4) 31.2 (3.4) 31.5 (3.6) | -17.2 (0.8) -18.8 (0.8) -11.7 (0.8) | -5.5 (-7.7, -3.4) -7.1 (-9.2, -5.0) | <0.0001 <0.0001 | |||||
Study 5b, e [MADRS] Non-US | vortioxetine tablets 5 mg vortioxetine tablets 10 mg vortioxetine tablets 20 mg Placebo | 142 147 149 150 | 31.6 (3.7) 31.8 (4.0) 31.7 (3.7) 31.6 (3.6) | -14.6 (0.8) -15.7 (0.8) -15.8 (0.8) -13.9 (0.8) | -0.6 (-3.3, 2.0) -1.7 (-4.3, 0.9) -1.8 (-4.4, 0.8) | NS | |||||
Study 6a, c [HAM-D24] US | vortioxetine tablets 5 mg Placebo | 292 286 | 32.7 (5.4) 32.1 (5.5) | -14.6 (0.7) -13.9 (0.7) | -0.74 (-2.5, 1.0) | NS | |||||
Study 7*b, c [HAM-D24] | vortioxetine tablets 5 mg | 153 | 29.8 (5.6) | -11.1 (0.7) | -0.6 (-2.6, 1.5) | NS | |||||
Study number [Primary Measure] | Treatment group | Number of patients | Mean baseline score (SD) | LS Mean change from baseline (SE) | LS Mean difference from placebo (95% CI) | p-value | |||||
| US | Placebo | 149 | 29.5 (6.1) | -10.5 (0.8) | |||||||
| Study 8*b, d [MADRS] US | vortioxetine tablets 15 mg vortioxetine tablets 20 mg Placebo | 145 147 153 | 31.9 (4.1) 32.0 (4.4) 31.6 (4.2) | -14.3 (0.9) -15.6 (0.9) -12.8 (0.8) | -1.5 (-3.9, 0.9) -2.8 (-5.1, -0.4) | NS 0.023 | |||||
| Study 9b, d [MADRS] US | vortioxetine tablets 10 mg vortioxetine tablets 20 mg Placebo | 154 148 155 | 32.3 (4.5) 32.5 (4.3) 32.0 (4.0) | -13.0 (0.8) -14.4 (0.9) -10.8 (0.8) | -2.2 (-4.5, 0.1) -3.6 (-5.9, -1.4) | NS 0.002 | |||||
| Study 10b, d [MADRS] US | vortioxetine tablets 10 mg vortioxetine tablets 15 mg Placebo | 143 142 149 | 34.1 (4.1) 33.7 (4.5) 33.4 (4.5) | -13.7 (1.1) -13.4 (1.1) -12.9 (1.0) | -0.79 (-3.7, 2.1) -0.5 (-3.4, 2.5) | NS | |||||
Study 11*b, c (elderly) [HAM-D24] Non-US & US | vortioxetine tablets 5 mg Placebo | 155 145 | 29.2 (5.0) 29.4 (5.1) | -13.7 (0.7) -10.3 (0.8) | -3.3 (-5.3, -1.3) | 0.0011 | |||||
* Study included active reference treatment
a Study duration 6 weeks
b Study duration 8 weeks
c Primary analysis model: ANCOVA using last observation carried forward, treatment and center as factors and baseline score as covariate
d Primary analysis model: MMRM using observed cases, baseline score as covariate
e Primary analysis ANCOVA model did not include site as covariate, results presented for post-hoc analysis using ANCOVA model including site as covariate.
NS = non-significant
SD = standard deviation
SE = standard error
CI = confidence interval
LS = least square
Long-term Maintenance of Effect
The efficacy of vortioxetine tablets in maintaining an antidepressant effect was assessed in a non-US trial including adult patients with MDD who initially responded to 12 weeks of acute open-label treatment with vortioxetine tablets. Patients in this study were 18 to 75 years of age, inpatients or outpatients who met DSM-IV-TR criteria for MDD and had a baseline MADRS total score > 26.
During the 12-week open label, acute treatment period patients received vortioxetine tablets 5 mg/day for the first 2 weeks. The dose could be increased to a 10 mg/day between Weeks 3 and 8 and decreased again to 5 mg/day during that time if needed. From Weeks 8 to 12 the dose remained fixed at 5 mg/day or 10 mg/day. Patients meeting the criterion for remission (MADRS total score < 10) at Weeks 10 and 12 were randomized to treatment with placebo or vortioxetine tablets (1:1) at the same dose received at the end of the open-label period, and observed for relapse for 24 to 64 weeks during a double-blind treatment period. The primary endpoint was the time to relapse during the first 24 weeks of the double-blind period. Relapse was defined as MADRS total score >22 or an unsatisfactory treatment effect (lack of efficacy) as judged by the investigator during the double-blind period.
The maintenance of antidepressant efficacy was demonstrated in a study in which patients in remission (MADRS total score <10) for the last 2 weeks of an initial 12-week open-label treatment period with vortioxetine tablets (5 or 10 mg/day) were randomized to vortioxetine tablets or placebo and observed for relapse during a double-blind period of at least 24 weeks (24 to 64 weeks). Prior to randomization, the dose of vortioxetine tablets was fixed at 5 mg/day or 10 mg/day for at least the last 4 weeks of the open label treatment period. For approximately 70% of randomized patients, the dose of vortioxetine tablets at the end of the open-label period and during the double-blind period was 10 mg/day. Vortioxetine tablets was superior (p=0.004) to placebo on the primary outcome measure, the time to relapse of MDD within the first 24 weeks of the double-blind period, with a hazard ratio of 2.0; that is, the risk of relapse was two times higher in the placebo group than in the vortioxetine tablets group.
14.2 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of APO-VORTIOXETINE 10 mg tablets, (Apotex Inc.) and prTRINTELLIX® 10 mg tablets (Lundbeck Canada Inc.) was conducted in healthy, adult, Asian Indian male subjects under fasting conditions. Comparative bioavailability data from 41 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Vortioxetine (1 x 10 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (ng.h/mL) | 201.79 204.94 (17.38) | 202.53 206.29 (19.15) | 99.6 | 96.8 – 102.6 |
Cmax (ng/mL) | 3.98 4.05 (17.79) | 4.05 4.13 (20.42) | 98.5 | 94.6 – 102.5 |
Tmax3 (h) | 10.00 (5.00 - 60.00) | 10.00 (5.00 – 60.65) | ||
1 APO-VORTIOXETINE (vortioxetine as vortioxetine hydrobromide) tablets, 10 mg (Apotex Inc.)
2 PrTRINTELLIX® (vortioxetine as vortioxetine hydrobromide) tablets, 10 mg (Lundbeck Canada Inc.)
3 Expressed as the median (range) only
Due to the long elimination half-life of vortioxetine, AUCI and T½ could not be accurately calculated from the data obtained in this study.
A randomized, two-way, single-dose, crossover comparative bioavailability study of APO-VORTIOXETINE 20 mg tablets (Apotex Inc.) and prTRINTELLIX® 20 mg tablets (Lundbeck Canada Inc.) was conducted in healthy, adult, Asian Indian male subjects under fasting conditions. Comparative bioavailability data from the 34 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOVAILABILITY DATA
Vortioxetine (1 x 20 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (ng.h/mL) | 433.98 450.17 (26.81) | 436.29 450.22 (25.22) | 99.5 | 95.9 - 103.2 |
Cmax (ng/mL) | 8.64 8.92 (23.87) | 8.67 8.90 (23.25) | 99.7 | 95.8 - 103.8 |
Tmax3 (h) | 8.00 (5.00 – 30.00) | 8.00 (6.00 – 30.00) | ||
1 APO-VORTIOXETINE (vortioxetine as vortioxetine hydrobromide) tablets, 20 mg (Apotex Inc.)
2 PrTRINTELLIX® (vortioxetine as vortioxetine hydrobromide) tablets, 20 mg (Lundbeck Canada Inc.)
3 Expressed as the median (range) only
Due to the long elimination half-life of vortioxetine, AUCI and T½ could not be accurately calculated from the data obtained in this study.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicity:
A comprehensive programme of toxicology studies ranging from single-dose studies up to 26- or 52-week repeat-dose toxicity, genotoxicity, carcinogenicity, and reproductive toxicity studies were conducted for vortioxetine.
Single-Dose/Acute Toxicity
The acute oral single dose toxicity of vortioxetine is relatively low with a maximum tolerated dose (MTD) in mice and rats of 300 and 500 mg/kg, respectively. Clinical signs consisted of marked sensitivity to touch and disturbance, rapid breathing, and brown perinasal staining in rats administered 500 mg/kg. In mice, tremors, sensitivity to touch, eyes partly closed, and hypoactivity were seen after 200 and 300 mg/kg, as well as rapid, noisy and/or labored breathing, incoordination, unsteady gait, leaning, salivation, and hyperactivity after 400 and 500 mg/kg. When administered as two vortioxetine doses given an hour apart (2 x ≥200 mg/kg), clinical signs were more severe, included convulsions, and resulted in death or necessitated euthanasia of moribund rats.
No formal acute toxicity studies were conducted in non-rodents. In a MTD study in dogs given 25 mg/kg/day for 1 week clinical signs of toxicity consisted of salivation, vomiting, abdominal muscle contractions, soft/liquid faeces, subdued behavior, sedation, stiff body and/or legs, pupil dilation, and reduced body weight and food consumption.
Repeat-Dose Toxicity
Administration of vortioxetine in the general toxicity studies in mice, rats and dogs was mainly associated with CNS-related clinical signs. Sporadic salivation generally occurred at all dose levels in rats and at higher dose levels in dogs. Pupil dilatation and impaired pupillary response were the main clinical effects in dogs occurring at all dose levels (≥3.75 mg/kg/day), presumably due to pharmacologic activity. More severe clinical signs in dogs were generally seen at higher dose levels in the 13-week study and included overactivity, unsteady or abnormal gait, prostration, excessive urination, and excitement, as well as convulsions in one dog at each of 10 and 15 mg/kg/day. While no convulsions were seen at the 7.5 mg/kg/day dose level, with a corresponding safety margin of >5 based on systemic (Cmax) exposure compared to the MRHD of 20 mg/day, one of the convulsions in the dog given 10 mg/kg/day occurred 23 hours post- dose when levels of vortioxetine and its metabolite were likely low.
Target organ toxicity was restricted to kidneys (male rats) and liver (mice and rats) and was mainly attributed to vortioxetine-related crystalline material obstruction of the renal tubules and the bile ducts, respectively, which is considered unlikely to occur in patients at therapeutic doses. The above findings were seen at exposures above those achieved during therapeutic use and considered of low risk to humans. The changes in rat kidney occurred at 80 mg/kg/day (40 mg/kg b.i.d.) and consisted of crystalline material in tubules/papilla/glomeruli, tubular basophilia/regenerative hyperplasia, dilatation of collecting ducts, tubular dilatation, papillary necrosis/foreshortening, hyperplasia of pelvic and/or papillary epithelium, tubular and/or papillary inflammation and interstitial fibrosis or glomerulonephritis, with systemic exposure (AUC0-24h) at the NOEL (40 mg/kg/day) 7 times that at the MRHD.
The NOEL for hepatobiliary toxicity (crystalline material in bile ducts, bile duct hyperplasia, and pericholangitis at 40 and 80 mg/kg/day (20 and 40 mg/kg b.i.d., respectively) in the 26 week rat study was 20 mg/kg/day (10 mg/kg b.i.d.) at which systemic exposure (AUC0-24h) was 1.6 and 2.3 times, in male and female rats, respectively, that at the MRHD. Increased liver weight, hepatocellular hypertrophy, and focal hepatocellular necrosis were also seen, generally at the same dose levels. There were no comparable renal or hepatic effects in dogs at any dose level.
Carcinogenicity:
CD-1 mice and Wistar rats were given oral doses of vortioxetine up to 50 and 100 mg/kg/day for male and female mice, respectively, and 40 and 80 mg/kg/day (administered as split doses up to 20 and 40 mg/kg b.i.d., respectively) for male and female rats, respectively, for 2 years. These doses in the two species were approximately 12, 24, 20, and 39 times, respectively, the
MRHD of 20 mg on a mg/m2 body surface area basis.
Vortioxetine is not considered to pose a significant risk of carcinogenicity in humans. Small increase in the incidences of hepatocellular adenomas in high dose male mice (50 mg/kg/day) and high dose male (40 mg/kg/day) and female (80 mg/kg/day) rats were considered to be due to chronic hepatotoxicity, which is not apparent in humans. In rats, the incidence of benign polypoid adenomas of the rectum was statistically significantly increased in females at doses 39 times the MRHD, but not at 15 times the MRHD. These were considered related to mucosal inflammation and hyperplasia in the large intestine and possibly due to exacerbation of an effect of the vehicle (hydroxypropyl- β-cyclodextrin) used for the study. A small statistically significant increase in the incidence of histiocytic sarcomas confined to high dose males (40 mg/kg/day) was considered incidental. A dose-dependent increased incidence of hemangiomas in the mesenteric lymph node of males at 14 and 40 mg/kg/day was also likely incidental, since there was no increase in hemangiosarcomas and vascular tumors were not seen in females or in any other tissue in rats which would generally be considered a more susceptible species for the development vascular tumors.
Genotoxicity:
Vortioxetine was not genotoxic in a standard battery of in vitro and in vivo tests that consisted of a bacterial mutagenicity assay, an in vitro cytogenetic assay conducted in human peripheral blood lymphocytes, and an in vivo male rat bone marrow micronucleus test with plasma concentrations, in terms of Cmax, of up to 44-fold for vortioxetine compared to the MRHD of 20 mg/day.
Reproductive and Developmental Toxicology:
Vortioxetine had no effect on rat fertility, mating performance, reproductive organs, or sperm morphology and motility at dose levels up to 120 mg/kg/day (60 mg/kg b.i.d.) at which plasma vortioxetine concentrations were 24 and 17 times that at the MRHD. Vortioxetine was not teratogenic in rats or rabbits at dose levels up to 160 and 60 mg/kg/day, respectively (80 and 30 mg/kg b.i.d.). However, reproductive toxicity in terms of effects on fetal weight and delayed ossification were seen in the rat at ≥30 mg/kg/day (≥15 mg/kg b.i.d.) with plasma concentrations at the 10 mg/kg/day (5 mg/kg b.i.d.) NOEL corresponding to about 6 times the Cmax at the MRHD of 20 mg/day. Similar developmental delays were seen in the rabbit at sub-therapeutic exposures.
In a pre- and post-natal study in rats, vortioxetine was associated with increased pup mortality, reduced body weight gain, and delayed pup development at doses that did not result in maternal toxicity and with associated systemic vortioxetine exposures similar to those achieved in humans following administration of vortioxetine 20 mg/day (see 7.1.1 Pregnant Women).
Vortioxetine-related material was distributed to the milk of lactating rats (see 7.1.2 Breast-feeding).
In juvenile toxicity studies in rats, all vortioxetine treatment-related findings were consistent with those noted in adult animals.
Special Toxicology:
Immunotoxicity
An immunotoxicity assessment as part of a vortioxetine 13-week toxicity study with 4-week recovery in Han Wistar rats revealed no immunotoxicity reactions based on lymphocyte immunophenotyping and natural killer cell function assays.
17 SUPPORTING PRODUCT MONOGRAPHS
1 TRINTELLIX® (Vortioxetine Tablets, 5 mg, 10 mg, 15 mg, and 20 mg vortioxetine [as vortioxetine hydrobromide]), submission control 274021, Product Monograph, Lundbeck Canada Inc. (MAY 27, 2024)