


Product Monograph - Bupivacaine Hydrochloride in Dextrose Injection USP (Formative Pharma)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Non-medicinal Ingredients |
|---|---|---|
| Spinal | Bupivacaine Hydrochloride in Dextrose Injection USP Sterile Solution 0.75% hyperbaric solution | Dextrose, sodium hydroxide and/or hydrochloric acid and water for injection. |
INDICATIONS AND CLINICAL USE
Adults (> 18 years of age):
Bupivacaine Hydrochloride in Dextrose Injection USP is indicated for the production of local or regional anaesthesia and analgesia with the following procedure:
- Subarachnoid (spinal) blocks
Standard procedures for subarachnoid (spinal) blocks should be observed.
Geriatrics (> 65 years of age):
Elderly patients should be given reduced doses commensurate with their age and physical condition.
Pediatrics (< 2 years of age):
Until further experience is gained in children younger than two years, administration of any presentation of bupivacaine injection in this age group is not recommended.
CONTRAINDICATIONS
Bupivacaine Hydrochloride in Dextrose Injection USP is contraindicated:
- In patients with a hypersensitivity to bupivacaine, or to any local anaesthetic agent of the amide type, or to other components of bupivacaine injection.
- In severe shock and in heart block and when there is inflammation and/or sepsis near the site of the proposed injection.
Spinal Use
With the exception of serious diseases of the central nervous system or of the lumbar vertebral column, most anesthesiologists consider the following conditions to be only relative contraindications to spinal anesthesia. The decision as to whether or not spinal anesthesia should be used for an individual case depends on the physician’s appraisal of the advantages, as opposed to the risks, and on his ability to cope with the complications that may arise.
- 1. Disease of the cerebrospinal system, such as meningitis, spinal fluid block, cranial or spinal hemorrhage, increased intracranial pressure, tumours and syphilis.
- 2. Shock. This should be treated before any anesthetic is administered. However, in emergency operations, spinal anesthesia may at times be considered the method of choice.
- 3. Profound anemia, cachexia and when death is imminent.
- 4. Sepsis with positive blood cultures.
- 5. High Blood Pressure. Spinal anesthesia should be well tolerated if particular care is taken to prevent a sudden or appreciable fall in blood pressure.
- 6. Low Blood Pressure. The use of suitable pressor agents and methods of controlling the diffusion of the anesthetic should remove the principal objection to spinal anesthesia in patients with low blood pressure.
- 7. Highly nervous and sensitive persons. Pre-operative medication should overcome this difficulty.
- 8. Visceral perforation, bowel strangulation, acute peritonitis. Some surgeons object to contraction of the gastrointestinal musculature; others, however, consider the associated arrest of peristalsis an advantage. With gastrointestinal hemorrhage, spinal anesthesia should be used with caution or may even be contraindicated.
- 9. Cardiac decompensation, massive pleural effusion and increased intra-abdominal pressure (e.g. full-term pregnancy, massive ascites, large tumor). High spinal anesthesia should not be used in patients with these conditions unless the Trendelenburg position can be omitted or the intra-abdominal pressure released slowly.
WARNINGS AND PRECAUTIONS
General
LOCAL ANAESTHETICS SHOULD ONLY BE USED BY CLINICIANS WHO ARE WELL VERSED IN DIAGNOSIS AND MANAGEMENT OF DOSE-RELATED TOXICITY AND OTHER ACUTE EMERGENCIES WHICH MAY ARISE FROM THE BLOCK TO BE PERFORMED, AND THEN ONLY AFTER ENSURING THE IMMEDIATE AVAILABILITY OF CARDIOPULMONARY RESUSCITATIVE EQUIPMENT, RESUSCITATIVE DRUGS, INCLUDING OXYGEN, AND THE PERSONNEL RESOURCES NEEDED FOR PROPER MANAGEMENT OF TOXIC REACTIONS AND RELATED EMERGENCIES (see ADVERSE REACTIONS AND OVERDOSAGE). DELAY IN PROPER MANAGEMENT OF DOSE- RELATED TOXICITY, UNDERVENTILATION FROM ANY CAUSE AND/OR ALTERED SENSITIVITY MAY LEAD TO THE DEVELOPMENT OF ACIDOSIS, CARDIAC ARREST AND, POSSIBLY, DEATH.
AN INTRAVENOUS CANNULA MUST BE INSERTED BEFORE THE LOCAL ANAESTHETIC IS INJECTED FOR NERVE BLOCKS WHICH MAY RESULT IN HYPOTENSION OR BRADYCARDIA, OR WHERE ACUTE SYSTEMIC TOXICITY MAY DEVELOP FOLLOWING INADVERTENT INTRAVASCULAR INJECTION.
THE LOWEST DOSAGE OF LOCAL ANAESTHETIC THAT RESULTS IN EFFECTIVE ANAESTHESIA OR ANALGESIA SHOULD BE USED TO AVOID HIGH PLASMA LEVELS AND SERIOUS ADVERSE REACTIONS. INJECTIONS SHOULD BE MADE SLOWLY OR IN INCREMENTAL DOSES, WITH FREQUENT ASPIRATIONS BEFORE AND DURING THE INJECTION TO AVOID INTRAVASCULAR INJECTION.
Cardiovascular
Ventricular arrhythmia, ventricular fibrillation, sudden cardiovascular collapse and death have been reported when bupivacaine was utilized for local anaesthetic procedures that may have resulted in high systemic concentrations of bupivacaine.
Subarachnoid (spinal) blocks may lead to hypotension and bradycardia. The risk of such effects can be reduced either by preloading the circulation with crystalloidal or colloidal solutions or by injecting a vasopressor such as ephedrine 20-40 mg i.m. Hypotension should be treated promptly, e.g., with ephedrine 5-10 mg intravenously and repeated as necessary. Children should be given ephedrine doses commensurate with their age and weight.
Local anaesthetics should be used with caution in patients with impaired cardiovascular function because they may be less able to compensate for functional changes associated with the prolongation of A-V conduction produced by amide-type local anaesthetics.
Patients with partial or complete heart block require special attention since local anaesthetics may depress myocardial conduction. To reduce the risk of potentially serious adverse reactions, attempts should be made to optimize the patient’s condition before major blocks are performed.
Dosage should be adjusted accordingly.
Subarachnoid (spinal) anaesthesia should be used with caution in patients with impaired cardiovascular function.
Spinal Use
In addition to the above noted precautions, when administering bupivacaine hyperbaric solution for spinal anesthesia, the patient’s blood pressure should be carefully monitored. Spinal anesthesia is usually associated with a fall in arterial blood pressure due to sympathetic blockade.
Hepatic
Because amide-type local anaesthetics such as bupivacaine are metabolized by the liver, these drugs should be used cautiously in patients with hepatic disease. Patients with severe hepatic disease, because of their inability to metabolize local anaesthetics normally, are at a greater risk of developing toxic plasma concentrations.
Peri-Operative Considerations
It is essential that aspiration for blood or cerebrospinal fluid be done prior to injecting any local anesthetic, both the original dose and all subsequent doses, to avoid intravascular or subarachnoid injection. During the performance of spinal anesthesia, a free flow of cerebrospinal fluid is indicative of entry into the subarachnoid space. Aspiration should be performed before the anesthetic solution is injected to confirm entry into the subarachnoid space and to avoid intravascular injection. However, a negative aspiration does not ensure against an intravascular or subarachnoid injection.
The safety and effectiveness of local anesthetics depend on proper dosage, correct technique, adequate precautions and readiness for emergencies. Regional or local anesthetic procedures should always be performed in a properly equipped and staffed area.
Resuscitative equipment and resuscitative drugs, including oxygen, should be available for immediate use (see WARNINGS AND PRECAUTIONS, and ADVERSE REACTIONS and OVERDOSAGE). During major regional nerve blocks, the patients should be in an optimal condition and have i.v. fluids running via an indwelling catheter to assure a functioning intravenous pathway. The clinician responsible should have adequate and appropriate training in the procedure to be performed, should take the necessary precautions to avoid intravascular injection (see DOSAGE AND ADMINISTRATION), and should be familiar with the diagnosis and treatment of side effects, systemic toxicity and other complications (see ADVERSE REACTIONS and OVERDOSAGE).
Careful and constant monitoring of cardiovascular and respiratory vital signs (adequacy of ventilation) and the patient’s state of consciousness should be performed after each local anaesthetic injection. It should be kept in mind at such times that restlessness, anxiety, incoherent speech, lightheadedness, numbness and tingling of the mouth and lips, metallic taste, tinnitus, dizziness, blurred vision, tremors, twitching, depression, or drowsiness may be early warning signs of central nervous system toxicity.
Renal
Local anaesthetics should be used with caution in patients in poor general condition due to severe renal dysfunction although regional anaesthesia is frequently indicated in these patients.
Special Populations
Debilitated and acutely ill patients should be given reduced doses commensurate with their age and physical condition.
Pregnant Women: Decrease pup survival in rats and an embryocidal effect in rabbits have been observed when bupivacaine hydrochloride was administered to these species in doses comparable, respectively, to nine and five times the maximal recommended daily human dose (400 mg).
There are no adequate and well-controlled studies in pregnant women of the effect of bupivacaine on the developing foetus.
Bupivacaine should be used during pregnancy only if the potential benefit justifies the potential risk to the foetus. This does not exclude the use of bupivacaine at term for obstetrical anaesthesia or analgesia.
Labour and Delivery: The 0.75% hyperbaric solution of Bupivacaine Hydrochloride in Dextrose Injection USP should be used for women during Labour and Delivery only if the potential benefit justifies the potential risk to the mother and foetus.
Maternal hypotension has resulted from regional anaesthesia (see WARNINGS AND PRECAUTIONS, Cardiovascular). Local anaesthetics produce vasodilation by blocking sympathetic nerves. It is extremely important to avoid aortocaval compression by the gravid uterus during administration of regional block to parturients. Elevating the patient’s legs and positioning her on her left side will help prevent decreases in blood pressure. The foetal heart rate also should be monitored continuously, and electronic foetal monitoring is highly advisable.
Subarachnoid anaesthesia may alter the forces of parturition through changes in uterine contractility or maternal expulsive efforts. Subarachnoid anaesthesia may prolong the second stage of labour by removing the parturient’s urge to bear down or by interfering with motor function. Obstetrical anaesthesia may increase the need for forceps assistance.
Nursing Women: Bupivacaine is excreted in the breast milk, but in such small quantities that there is generally no risk of affecting the infant at therapeutic doses.
Pediatrics: Until further experience is gained in children younger than two years, administration of any presentation of bupivacaine injection in this age group is not recommended.
Until further experience is gained, Bupivacaine Hydrochloride in Dextrose Injection USP (bupivacaine hydrochloride 0.75% hyperbaric solution in dextrose) is not recommended for spinal use in patients younger than 18 years.
Geriatrics: Elderly patients should be given reduced doses commensurate with their age and physical condition.
ADVERSE REACTIONS
Reactions to bupivacaine hydrochloride are characteristic of those associated with other local acting anesthetics of the amide type.
Adverse reactions to local anaesthetics are very rare in the absence of overdose or inadvertent intravascular injection. The effects of systemic overdose and unintentional intravascular injections can be serious, but should be distinguished from the physiological effects of the nerve block itself (e.g. a decrease in blood pressure and bradycardia during epidural anaesthesia). Neurological damage, caused directly (e.g. nerve trauma) or indirectly (e.g. epidural abscess) by the needle puncture, is a rare but well recognised consequence of regional, and particularly epidural anaesthesia.
The most commonly encountered acute adverse experiences that demand immediate management are related to the central nervous system and the cardiovascular system. These adverse reactions are generally dose-related and due to high plasma levels which may result from overdosage (see OVERDOSAGE), rapid absorption from the injection site, diminished tolerance or from inadvertent intravascular injection. Factors influencing plasma protein binding, e.g. diseases which alter protein synthesis or competition of other drugs for protein binding, may diminish individual tolerances.
In addition to systemic dose-related toxicity, unintentional subarachnoid injection of drug during the intended performance of caudal or lumbar epidural block or nerve blocks near the vertebral column (especially in the head and neck region) may result in under ventilation or apnoea (“Total or High Spinal”). Also, hypotension due to loss of sympathetic tone and respiratory paralysis or underventilation due to cephalad extension of the motor level of anaesthesia may occur. This may lead to secondary cardiac arrest if untreated.
Central Nervous System: Restlessness, anxiety, dizziness, tinnitus, blurred vision or tremors may occur, possibly proceeding to convulsions. However, excitement may be transient or absent, with depression being the first manifestation of an adverse reaction. This may quickly be followed by drowsiness merging into unconsciousness and respiratory arrest. Other central nervous system effects may be nausea, vomiting, chills, paraesthesia, numbness of the tongue, hyperacousis, lightheadedness, dysarthria and constriction of the pupils.
Cardiovascular System: High doses or unintentional intravascular injection may lead to high plasma levels and related depression of the myocardium, decreased cardiac output, heart block, hypotension, bradycardia, hypertension, ventricular arrhythmias, including ventricular tachycardia and ventricular fibrillation, and cardiac arrest. Reactions due to systemic absorption may be either slow or rapid in onset. Cardiovascular collapse and cardiac arrest can occur rapidly (see WARNINGS AND PRECAUTIONS, Cardiovascular and OVERDOSAGE sections).
Allergic: Allergic type reactions are rare (<0.1%) and may occur as a result of sensitivity to local anaesthetics of the amide type. These reactions are characterized by signs such as urticaria, pruritus, erythema, angioneurotic oedema (including laryngeal oedema), tachycardia, sneezing, nausea, vomiting, dizziness, syncope, excessive sweating, elevated temperature, and in the most severe instances, anaphylactic shock.
Neurologic: The incidence of adverse neurologic reactions may be related to the total dose of local anaesthetic administered but is also dependent upon the particular drug used, the route of administration and the physical condition of the patient. Nerve trauma, neuropathy, urinary retention, diplopia and spinal cord dysfunction (e.g., anterior spinal artery syndrome, arachnoiditis, cauda equina syndrome, in rare cases paresis and paraplegia), have been associated with regional anaesthesia. Neurological effects may be related to local anaesthetic techniques, with or without a contribution from the drug.
High or Total Spinal Blockade: In the practice of caudal or lumbar epidural block, occasional unintentional penetration of the subarachnoid space by the catheter may occur, resulting in High or Total Spinal Blockage. Subsequent adverse effects may depend partially on the amount of drug administered subdurally.
Extensive loss of motor and sensory functions, loss of consciousness and cardiovascular and respiratory depression may happen. The cardiovascular depression is caused by extensive sympathetic blockade which may result in profound hypotension and bradycardia, or even cardiac arrest. Respiratory depression is caused by blockade of the innervation of the respiratory muscles, including the diaphragm.
Spinal Use: THE MOST COMMONLY ENCOUNTERED ADVERSE REACTIONS WHICH DEMAND IMMEDIATE COUNTERMEASURES ARE HYPOTENSION DUE TO LOSS OF SYMPATHETIC TONE AND RESPIRATORY PARALYSIS OR UNDERVENTILATION DUE TO CEPHALAD EXTENSION OF THE MOTOR LEVEL OF ANESTHESIA. THESE MAY LEAD TO CARDIAC ARREST IF UNTREATED.
In addition, one or several of the following complications or side effects may be observed during or after spinal anesthesia.
Meningitis
With the employment of an aseptic technique, septic meningitis should be practically nonexistent. Some instances of aseptic meningitis, with fever, neck rigidity, and cloudy spinal fluid, have been reported with the use of other spinal anesthetics. In such cases, the course is usually brief and benign, terminating in complete recovery.
However, in a few, permanent paralyses (sometimes terminating fatally) and sensory disturbances have been observed. This type of meningitis has also been observed in rare instances following ordinary diagnostic lumbar puncture.
Palsies
These are rare and affect either the extraocular muscles or the legs and the anal and vesical sphincters (cauda equina syndrome). Paralysis of extraocular muscles usually clears up spontaneously by the third or fourth week.
Clauda equina and lumbosacral cord complications (usually consisting of arachnoiditis and demyelinization) result in loss of impairment of motor and sensory function of the saddle area (bladder, rectum) and one or both legs. The complications have occurred after the use of most, if not all, spinal anesthetics. The loss or impairment of motor function may be permanent or partial recovery may slowly occur. Various explanations for such complications have been advanced, such as hypersensitivity or intolerance to the anesthetic agent with a resultant myelolytic or neurotoxic effect; pooling of relatively high concentrations of anesthetic solution around the cauda equina and spinal cord before diffusion; and accidental injection of irritating antiseptics or detergents (as when syringes and needles are incompletely cleansed or when ampoule storage enters a cracked ampoule). Hence, most anesthesiologists prefer to autoclave ampoules in order to destroy bacteria on the exterior before opening.
Headache
This may largely be prevented by using a small gauge needle to prevent spinal fluid leakage and by placing the patient in the supine position after operation and providing adequate hydration.
Nausea and Vomiting
These may be due to a drop in blood pressure, undue intra-abdominal manipulation or preoperative medication.
DRUG INTERACTIONS
Drug-Drug Interactions
Bupivacaine should be used cautiously in persons with known drug allergies or sensitivities.
Local anaesthetics
Mixing or the prior or intercurrent use of any other local anesthetic with bupivacaine is not recommended because of insufficient data regarding the interaction and safety of such mixtures. Bupivacaine should be used with caution in patients receiving other amide-type local anaesthetics such as lidocaine, ropivacaine, mepivicaine and prilocaine since the toxic effects are additive.
Antiarrhythmic Drugs
Bupivacaine should also be used with caution with structurally related agents such as the antiarrhythmics, procainamide, disopyramide, tocainide, mexiletine and flecainide.
Class III Antiarrhythmic drugs
Specific interaction studies with bupivacaine and class III anti-arrhythmic drugs (e.g. amiodarone) have not been performed, but caution is advised. Patients being treated with class III anti-arrhythmic drugs should be under close surveillance and ECG monitoring since cardiac affects may be additive.
Bupivacaine with epinephrine or other vasopressors or vasoconstrictors should not be used concomitantly with ergot-type oxytocic drugs, because a severe persistent hypertension may occur and cerebrovascular and cardiac accidents are possible.
Monoamine Oxidase (MAO) Inhibitors
The administration of local anesthetic solutions containing epinephrine or norepinephrine to patients receiving monoamine oxidase inhibitors or tricyclic antidepressants may produce severe, prolonged hypertension. Concurrent use of these agents should generally be avoided. In situations when concurrent therapy is necessary, extreme caution and careful patient monitoring is essential.
Tricyclic Antidepressants (triptyline, imipramine)
The administration of local anesthetic solutions containing epinephrine or norepinephrine to patients receiving tricyclic antidepressants may produce severe, prolonged hypertension. Concurrent use of these agents should generally be avoided. In situations when concurrent therapy is necessary, extreme caution and careful patient monitoring is essential.
Neuroleptics (phenothiazines, butyrophenones)
Phenothiazines and butyrophenones may reduce or reverse the pressor effect of epinephrine resulting in hypotensive responses and tachycardia.
Sedatives
If sedatives are used to reduce patient apprehension, they should be used in reduced doses, since local anaesthetic agents, like sedatives, are central nervous system depressants which in combination may have an additive effect.
General Anaesthetics- Inhalation agents (halothane, cyclopropane, trichloroethylene, enflurane and related agents)
Dose-related cardiac arrhythmias may occur if preparations containing epinephrine are employed in patients during or immediately following the administration of general anaesthesia with inhalational agents such as halothane, cyclopropane, trichloroethylene, enflurane or other related agents. In deciding whether to use these products concurrently in the same patient, the combined action of both agents upon the myocardium, the concentration and volume of vascoconstrictor used, and the time since injection, when applicable, should be taken into account.
Use of chloroprocaine or other local anaesthetics, prior to general anesthesia, may interfere with subsequent use of bupivacaine. Because of this, and because safety of intercurrent use with bupivacaine and other local anaesthetics has not been established, such use is not recommended.
H2-antagonists
The H2-antagonists cimetidine and ranitidine have been shown to reduce the clearance of bupivacaine; ranitidine to a lesser degree than cimetidine. Concomitant administration may increase likelihood of toxicity of bupivacaine. Administration of H2 blockers prior to epidural anesthesia is inadvisable since toxic levels of local anesthetic may result.
Drug-Food Interactions
Interactions of bupivacaine with food have not been established.
Drug-Herb Interactions
Interactions of bupivacaine with herbal products have not been established.
Drug-Laboratory Interactions
Interactions of bupivacaine with laboratory tests have not been established.
Drug-Lifestyle Interactions
Interactions of bupivacaine with lifestyle have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
General
As with all local anesthetics, the dosage of bupivacaine varies and depends upon the area to be anesthetized, the vascularity of the tissues, the number of neuronal segments to be blocked, the depth of anesthesia and degree of muscle relaxation required, individual tolerance, the technique of anesthesia and the physical condition of the patient. The lowest dosage and concentration needed to provide effective anesthesia should be administered. The rapid injection of a large volume of local anaesthetic solution should be avoided and fractional doses should be used when feasible. In general, complete block of all nerve fibres in large nerves requires the higher concentrations of drug. In smaller nerves, or when a less intense block is required (e.g., in the relief of labour pain), the lower concentrations are indicated. The volume of drug used will affect the extent of spread of anaesthesia.
There have been adverse event reports of irreversible chondrolysis in patients receiving intraarticular infusions of local anesthetics following arthroscopic and other surgical procedures. Bupivacaine Hydrochloride in Dextrose Injection USP is not approved for this use (see WARNINGS AND PRECAUTIONS, General).
Special Populations
Local anaesthetics should be used with caution in patients in poor general condition due to aging or other compromising factors such as advanced liver disease or severe renal dysfunction although regional anaesthesia is frequently indicated in these patients.
Debilitated, elderly patients and acutely ill patients should be given reduced doses commensurate with their age and physical condition.
Recommended Dose and Dosage Adjustment
The duration of anesthesia with bupivacaine is such that, for most procedures, a single dose is sufficient. Maximum dosage limit must be individualized in each case after evaluating the size and physical status of the patient, as well as the usual rate of systemic absorption from a particular injection site. The maximum doses of bupivacaine are considered to apply to a healthy 70 kilogram, young male. However, it is not recommended that they be exceeded in heavier persons.
At present, there is insufficient clinical evidence with multiple dosage or intermittent dose techniques to permit precise recommendations for such procedures to be given.
The 0.75% hyperbaric solution of Bupivacaine Hydrochloride in Dextrose Injection USP is recommended at term for obstetrical anesthesia and analgesia.
To avoid intravascular injection, aspiration should be repeated prior to and during administration of the main dose, which should be injected slowly, while closely observing the patient’s vital functions and maintaining verbal contact.
Adults:
Dosage and administration of Bupivacaine Hydrochloride in Dextrose Injection USP should be managed according to the patient condition and standard of anaesthetic care. See Spinal Use.
Children:
Until further experience is gained, bupivacaine is not recommended for children younger than two years of age. The following restriction applies to the use of Bupivacaine Hydrochloride in Dextrose Injection USP for children over two years of age: Bupivacaine Hydrochloride in Dextrose Injection USP is not recommended for spinal use in patients younger than 18 years.
Spinal Use
Bupivacaine for spinal anesthesia is available as a 0.75% hyperbaric solution.
The smallest dose required to produce the desired result should be administered and the dosage should be reduced for elderly and debilitated patients and patients with cardiac and/or liver disease. The use of the hyperbaric solution should permit improved control of the extent of anesthesia since the solution will have a higher specific gravity than spinal fluid.
Bupivacaine Hydrochloride in Dextrose Injection USP (0.75% hyperbaric solution) is not recommended in patients younger than 18 years of age.
| RECOMMENDED ADULT DOSAGE LIMITS FOR SPINAL ANESTHESIA | |||
|---|---|---|---|
| Extent of Anesthesia | Bupivacaine Hydrochloride in Dextrose Injection USP (0.75% Hyperbaric Solution) Dosage | Injection Site (Lumbar Interspace) | |
| mL | mg | ||
| Low Spinal and Saddle block for perineal operations | 0.8 - 1.06 | 6 - 8 | 4th |
| Median Spinal for operations on lower abdomen | 1.06 - 1.6 | 8 - 12 | 3rd or 4th |
| High Spinal for operations on upper abdomen | 1.6 - 2.0 | 12 - 15 | 2nd, 3rd or 4th |
The extent and degree of spinal anesthesia depend on: the dose of anesthetic (see table), the specific gravity of the anesthetic solution, the volume of solution administered, the force of injection, the level of puncture and the position of the patient during and immediately after injection.
The lateral recumbent position is the customary one for injection; however, when both perineal and abdominal anesthesia are required, the sitting position may be preferred. After preliminary antiseptic preparation of the back, the spinal interspace to be punctured is marked and anesthetized with 1 to 2 mL of 0.25% bupivacaine HCl solution.
Ephedrine (25 mg) may be administered if needed to maintain blood pressure.
After the spinal anesthetic has been administered, the specific gravity of the solution injected determines which position the patient should be placed in, at least for the first 15 to 20 minutes. Continuous sensory tests should be made by gentle strokes with a sharp instrument or by pinching the skin, comparing the sensitivity to that of the inside of the forearm.
Since hypalgesia always precedes anesthesia, it is necessary to determine the line of demarcation between hypalgesia and normal sensation, to avoid extension of anesthesia above the desired segment.
After injection of a 0.75% hyperbaric solution for spinal anesthesia, the patient is immediately placed on his back and the table tilted to a 10 to 20 degree Trendelenburg position in order to allow the solution to flow cephalad.
Under no circumstances should a patient be left in a head-down position longer than one minute from the start of injection without testing the height of anesthesia. The neck is sharply flexed by supporting the head on a double pillow. When hypalgesia is extended to the desired height, the table is promptly brought to the horizontal position and time (about 10 to 20 minutes) allowed for the anesthetic agent to become fixed.
OVERDOSAGE
Acute systemic toxicity from local anaesthetics is generally related to high plasma levels encountered during therapeutic use of local anesthetics, or to unintended subarachnoid or intravascular injection, exceptionally rapid absorption from highly vascularized areas or overdosage and originates mainly in the central nervous and the cardiovascular systems (see ADVERSE REACTIONS and WARNINGS AND PRECAUTIONS). Central nervous system reactions are similar for all amide local anaesthetics, while cardiac reactions are more dependent on the drug, both quantitatively and qualitatively.
Symptoms
Accidental intravascular injections of local anaesthetics may cause immediate (within seconds to a few minutes) systemic toxic reactions. In the event of overdose, systemic toxicity appears later (15-60 minutes after injection) due to the slower increase in local anaesthetic blood concentration.
Central nervous system toxicity is a graded response with symptoms and signs of escalating severity. The first symptoms are usually circumoral paresthesia, numbness of the tongue, lightheadedness, hyperacousis, tinnitus and visual disturbances. Dysarthria, muscular twitching or tremors are more serious and precede the onset of generalized convulsions. These signs must not be mistaken for a neurotic behaviour. Unconsciousness and grand mal convulsions may follow which may last from a few seconds to several minutes. Hypoxia and hypercarbia occur rapidly following convulsions due to the increased muscular activity, together with the interference with normal respiration and loss of the airway. In severe cases apnoea may occur. Acidosis, hyperkalaemia, hypocalcaemia and hypoxia increase and extend the toxic effects of local anaesthetics.
Recovery is due to redistribution and subsequent metabolism and excretion of the local anaesthetic drug. Recovery may be rapid unless large amounts of the drug have been administered.
Cardiovascular system toxicity may be seen in severe cases and is generally preceded by signs of toxicity in the central nervous system. In patients under heavy sedation or receiving a general anaesthetic, prodromal CNS symptoms may be absent. Hypotension, bradycardia, arrhythmia and even cardiac arrest may occur as a result of high systemic concentrations of local anaesthetics, but in rare cases cardiac arrest has occurred without prodromal CNS effects.
Cardiovascular toxic reactions are usually related to depression of the conduction system of the heart and myocardium, leading to decreased cardiac output, hypotension, heart block, bradycardia and sometimes ventricular arrhythmias, including ventricular tachycardia, ventricular fibrillation and cardiac arrest.
In children, early signs of local anaesthetic toxicity may be difficult to detect in cases where the block is given during general anaesthesia.
Treatment
The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient’s state of consciousness after each local anesthetic injection. At the first sign of change, oxygen should be administered. If signs of acute systemic toxicity appear, injection of the local anaesthetic should be immediately stopped.
THE FIRST STEP IN THE MANAGEMENT OF SYSTEMIC TOXIC REACTIONS, AS WELL AS UNDERVENTILATION OR APNEA, CONSISTS OF THE IMMEDIATE ESTABLISHMENT AND MAINTENANCE OF A PATENT AIRWAY AND ASSISTED OR CONTROLLED VENTILATION WITH 100% OXYGEN AND A DELIVERY SYSTEM CAPABLE OF PERMITTING IMMEDIATE POSITIVE AIRWAY PRESSURE BY MASK OR ENDOTRACHEAL INTUBATION. This may prevent convulsions if they have not already occurred.
Supportive treatment of the cardiovascular system includes intravenous fluids and, when appropriate, vasopressors (such as epinephrine or ephedrine which enhance myocardial contractility).
If necessary, use drugs to control convulsions. A bolus i.v. injection of a muscle relaxant (e.g., succinylcholine 1 mg/kg bw) will paralyze the patient without depressing the central nervous or cardiovascular systems and facilitate endotracheal intubation, controlled ventilation, and secure optimal oxygenation. An anticonvulsant should be given i.v. if the convulsions do not stop spontaneously in 15-20 seconds. A bolus i.v. dose of diazepam (0.1 mg/kg) or thiopental (1-3 mg/kg) will permit ventilation and counteract central nervous system stimulation, but these drugs also depress central nervous system, respiratory, and cardiac function, add to possible depression, and may result in apnea. Thiopental will control convulsions rapidly, while the action of diazepam will be slower. Prolonged convulsions may jeopardize the patient’s ventilation and oxygenation. Intravenous barbiturates, anticonvulsant agents, or muscle relaxants should only be administered by those familiar with their use. For specific techniques and procedures, refer to standard textbooks.
Recent clinical data from patients experiencing local anesthetic-induced convulsions demonstrated rapid development of hypoxia, hypercarbia and acidosis with bupivacaine within a minute of the onset of convulsions. These observations suggest that oxygen consumption and carbon dioxide production are greatly increased during local anesthetic convulsions and emphasize the importance of immediate and effective ventilation with oxygen which may avoid cardiac arrest.
If cardiovascular depression is evident (hypotension, bradycardia), ephedrine 5-10 mg i.v. should be given and may be repeated, if necessary, after 2-3 minutes. Children should be given ephedrine doses commensurate with their age and weight.
Should circulatory arrest occur, immediate cardiopulmonary resuscitation should be instituted. Optimal oxygenation and ventilation and circulatory support as well as treatment of acidosis are of vital importance, since hypoxia and acidosis will increase the systemic toxicity of local anaesthetics. A successful resuscitation may require prolonged efforts.
The supine position is dangerous in pregnant women at term because of aortocaval compression by the gravid uterus. Therefore, during treatment of systemic toxicity, maternal hypotension or foetal bradycardia following regional block, the parturient should be maintained in the left lateral decubitus position if possible, or manual displacement of the uterus off the great vessels should be accomplished. Resuscitation of obstetrical patients may take longer than resuscitation of nonpregnant patients and closed-chest cardiac compression may be ineffective. Rapid delivery of the foetus may improve the response to resuscitative efforts.
If cardiac arrest should occur, a successful outcome may require prolonged resuscitative efforts.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
ACTION AND CLINICAL PHARMACOLOGY
Bupivacaine is a long-acting, amide-type local anaesthetic with both anaesthetic and analgesic effects. At high doses it produces surgical anaesthesia, while at lower doses it produces sensory block (analgesia) with less pronounced motor block.
Mechanism of Action
Bupivacaine stabilizes the neuronal membrane and prevents both the generation and the conduction of nerve impulses, thereby exerting a local anesthetic action. As with other local anaesthetics, bupivacaine causes a reversible blockade of impulse propagation along nerve fibres by preventing the inward movement of sodium ions through the cell membrane of the nerve fibres. The sodium channel of the nerve membrane is considered a receptor for local anaesthetic molecules.
Onset and Duration of Action
The onset of action is rapid, and anesthesia is long lasting. The duration of action of a local anesthetic is dependent on a number of factors including site of injection, route of administration, concentration and volume (see DOSAGE AND ADMINISTRATION). It has also been noted that there is a period of analgesia that persists after the return of sensation, during which time the need for strong analgesics is reduced.
Hemodynamics
Bupivacaine, like other local anaesthetics, may also have effects on other excitable membranes e.g. in the brain and myocardium. If excessive amounts of drug reach the systemic circulation rapidly, symptoms and signs of toxicity will appear, emanating mainly from the central nervous and cardiovascular systems.
Central nervous system toxicity (see OVERDOSAGE) usually precedes the cardiovascular effects as central nervous system toxicity occurs at lower plasma concentrations. Direct effects of local anaesthetics on the heart include slow conduction, negative inotropism and eventually cardiac arrest.
Indirect cardiovascular effects (hypotension, bradycardia) may occur after epidural administration depending on the extent of the concomitant sympathetic block.
Pharmacokinetics
Absorption: The plasma concentration of local anaesthetics is dependent upon the dose, the route of administration, the patient's hemodynamic/circulatory condition, and the vascularity of the injection site. The addition of epinephrine to bupivacaine may decrease the peak plasma concentration, whereas the time to peak plasma concentration usually is little affected. The effect varies with the type of block, dose and concentration.
Following injection of bupivacaine for caudal, epidural, or peripheral nerve block in man, peak levels of bupivacaine in the blood are reached in 30 to 45 minutes, followed by a gradual decline to insignificant levels during the next three to six hours. Intercostal blocks give the highest peak plasma concentration due to a rapid absorption (maximum plasma concentrations in the order of 1-4 mg/L after a 400 mg dose), while subcutaneous abdominal injections give the lowest plasma concentration. Epidural and major plexus blocks are intermediate. In children, rapid absorption and high plasma concentrations (in the order of 1-1.5 mg/L after a dose of 3 mg/kg) are seen with caudal block.
Bupivacaine shows complete, biphasic absorption from the epidural space with plasma half-lives in the order of seven minutes after initial administration, slowing to six hours over time. The slow absorption is rate-limiting in the elimination of bupivacaine, which explains why the apparent elimination half-life after epidural administration is longer than after intravenous administration.
Distribution: Local anesthetics are bound to plasma proteins in varying degrees. The highly lipophilic agents, such as bupivacaine, are far more highly protein-bound than the more hydrophilic compounds. Bupivacaine is approximately 95% protein-bound in normal adults. Generally, the lower the plasma concentration of drug, the higher the percentage of drug bound to plasma proteins. If plasma protein concentrations are decreased, more of the free drug will be available to exert activity. Bupivacaine is mainly bound to alpha-1-acid glycoprotein.
Bupivacaine readily crosses the placenta and equilibrium in regard to the unbound concentration is rapidly reached. The rate and degree of diffusion is governed by (1) the degree of plasma protein binding, (2) the degree of ionization and (3) the degree of lipid solubility. The degree of plasma protein binding in the foetus is less than in the mother, which results in lower total plasma concentrations in the foetus than in the mother. The free concentration, however, is the same in both mother and foetus.
Fetal/maternal ratios of local anesthetics appear to be inversely related to the degree of plasma protein binding because only the free, unbound drug is available for placental transfer. Bupivacaine with a high protein binding capacity (95%) has a low fetal/maternal ratio (0.2 to 0.4).
Bupivacaine has a total plasma clearance of 0.58 L/min a volume of distribution at steady state of 73 L.
An increase in total plasma concentration has been observed during continuous epidural infusion for postoperative pain relief. This is related to a postoperative increase in alpha-1-acid glycoprotein. The unbound, i.e. pharmacologically active, concentration is similar before and after surgery.
Metabolism: Because of its amide structure, bupivacaine is extensively metabolized in the liver predominantly by aromatic hydroxylation to 4-hydroxy-bupivacaine and N-dealkylation to 2,6- pipecoloxylidine (PPX), both mediated by cytochrome P450 3A4. The major metabolite of bupivacaine is pipecoloxylidine, a dealkylated derivative. Patients with hepatic disease may be more susceptible to the potential toxicities of the amide-type local anesthetics.
Excretion: The plasma elimination half-life of bupivacaine in adults is 2.7 hours (range 1.2 to 4.6 hours). In infants, the half-life ranges from 6 to 22 hours, thus it is significantly longer than in adults. Half-life is also prolonged in the elderly. Bupivacaine has an intermediate hepatic extraction ratio of 0.38 after i.v. administration. In children between 1 to 7 years the pharmacokinetics are similar to those in adults.
The kidney is the main excretory organ for most local anesthetics and their metabolites. Urinary excretion is affected by renal perfusion and factors affecting urinary pH.
Clearance of bupivacaine is almost entirely due to liver metabolism and more sensitive to changes in intrinsic hepatic enzyme function than to liver perfusion.
STORAGE AND STABILITY
Store Bupivacaine Hydrochloride in Dextrose Injection USP at 15-30°C.
SPECIAL HANDLING INSTRUCTIONS
Bupivacaine Hydrochloride in Dextrose Injection USP may be autoclaved. Autoclave at 15-pound pressure, 121°C (250°F) for 15 minutes. Do not use product if solution shows haziness, particulate matter, discolouration, or leakage.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Forms
Bupivacaine Hydrochloride in Dextrose Injection USP is a sterile solution.
The solubility of bupivacaine is limited at pH > 6.5. This must be taken into consideration when alkaline solutions, i.e., carbonates, are added since precipitation might occur.
Composition and Packaging
0.75% - hyperbaric solution for spinal use only
Bupivacaine Hydrochloride in Dextrose Injection USP spinal solution is supplied in 2 mL fill volume, single dose, preservative free ampoules containing 0.75% hyperbaric solution and is packaged into cartons containing 10 ampules each.
Each mL of solution contains 7.5 mg bupivacaine hydrochloride and 82.5 mg dextrose anhydrous in Water for Injection. The pH is adjusted between 4.0 and 6.5 with NaOH or HCl. The solution may be autoclaved once at 15-pound pressure, 121°C (250°F) for 15 minutes. Do not administer any solution which shows haziness, particulate matter, discolouration, or leakage.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Bupivacaine Hydrochloride
Proper Name:
Bupivacaine
Chemical Name:
2-Piperidinecarboxamide, 1-butyl-N-(2,6-dimethylphenyl), monohydrochloride, monohydrate, (±)
Molecular formula and molecular mass:
C18H28N2O•HCl•H2O 342.9 g/mol
Structural Formula:
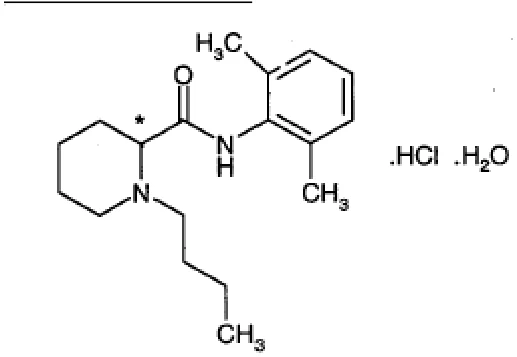
Physiochemical Properties:
White crystalline powder that is soluble in water, freely soluble in ethanol and slightly soluble in chloroform and acetone. Slightly hygroscopic with a melting point of 258.5°C.
DETAILED PHARMACOLOGY
Local anesthetics block the generation and the conduction of nerve impulses, presumably by increasing the threshold for electrical excitation in the nerve, by slowing the propagation of the nerve impulse, and by reducing the rate of rise of the action potential. In general, the progression of anesthesia is related to the diameter, myelination, and conduction velocity of affected nerve fibers. Clinically, the order of loss of nerve function is as follows: (1) pain, (2) temperature, (3) touch, (4) proprioception, and (5) skeletal muscle tone.
After injection of bupivacaine for caudal, epidural or peripheral nerve block in man, peak blood levels were reached in 30 to 45 minutes, followed by a decline to insignificant levels in the next 3 to 6 hours.
In metabolic studies in the rat, subcutaneous doses of C14 - labelled bupivacaine were rapidly absorbed. The gastrointestinal tract, liver, spleen and kidney showed relatively high concentrations. Radioactivity in adipose tissue was high immediately after drug administration but decreased rapidly and was not detected at 24 hours.
The principal route of biotransformation in the rat is by conjugation with glucuronic acid. Because of its amide structure, bupivacaine is not detoxified by plasma esterases.
As for other local anaesthetics, bupivacaine is metabolized in the liver predominantly by aromatic hydroxylation to 4-hydroxy-bupivacaine and N-dealkylation to 2,6-pipecoloxylidine (PPX), both mediated by cytochrome P450 3A4. The metabolites have a pharmacological activity that is less than that of bupivacaine. Bupivacaine and the metabolites are excreted mainly via the kidneys.
TOXICOLOGY
Acute LD50 determinations in the mouse and rat were as follows:
| Route of Administration | Species | Acute LD50 ± s.e. mg/kg at 24 hours | |
|---|---|---|---|
Bupivacaine HCl 0.75% (Hyperbaric) | I.V. | Mouse | 6.2 ± 0.4 |
At high intravenous doses in mice and rats, symptoms of toxicity included CNS stimulation followed by convulsions. Central stimulation is followed by depression and death is usually due to respiratory depression.
Bupivacaine produced seizures in rhesus monkeys when serum levels reached the 4.5 to 5.5 mcg/mL range.
No significant pathologic changes were observed following sub-lethal doses of bupivacaine in the rat, rabbit, dog and monkey, except for dose-related inflammatory reactions in the muscle tissue at the injection sites. In irritation studies in the rabbit, healing of the intramuscular lesions was well advanced or complete within seven days after the injection.
Libelius and others reported denervation-like changes in the skeletal muscle of rats following repeated intramuscular injection into the same site. They commented, however, that the conditions under which these changes occurred are not likely to be encountered in the clinical use of the drug.
No immediate or delayed allergic responses were observed in the guinea pig after sensitivity testing. No evidence of drug-induced teratogenic effects was observed in rats and rabbits given subcutaneous injections of bupivacaine.
Decreased pup survival in rats and an embryocidal effect in rabbits have been observed when bupivacaine hydrochloride was administered to these species in doses comparable to nine and five times, respectively the maximal recommended daily human dose (400 mg).
REFERENCES
- 1. Beazley JM, Taylor G, Reynolds, F. Placental transfer of bupivacaine after paracervical block. Obstet Gynecol 1972 Jan; 39(1):2-6.
- 2. Bailie D, Ellenbecker T. Severe chondrolysis after shoulder arthroscopy: A case series. J Should Elbow Surg 2009;18(5):742-747.
- 3. Blaise GA, Roy WL. Spinal anesthesia for minor paediatric surgery. Can Anaesth Soc J 1986 Mar; 33(2):227-30.
- 4. Broadman LM, Hanallah RS, Norden JM. “Kiddie Caudals”:Experience with 1154 consecutive cases without complications. Anesth Analg 1987; 66:848-54.
- 5. Bromage PR. An evaluation of bupivacaine in epidural analgesia for obstetrics. Can Anaesth Soc J. 1969 Jan; 16(1):46-56
- 6. Bromage PR. A comparison of bupivacaine and tetracaine in epidural analgesia for surgery. Can Anaesth Soc J. 1969 Jan; 16(1):37-45.
- 7. Brown RA and Catton DV. Use of bupivacaine in labour. Can Anaesth Soc J 1971 Jan; 18(1): 23-32.
- 8. Carolan JA, Cerasoli JR, Houle TV. Bupivacaine in retrobulbar anesthesia. Ann Ophthalmol. 1974 Aug; 6(8):843
- 9. Cartwright PD, McCarroll SM, Antzaka C. Maternal heart rate changes with a plain epidural test dose. Anesthesiology 1986 Aug; 65(2):226.
- 10. Dain SL, Rolbin SH, Hew EM. The epidural test dose in obstetrics: Is it necessary? Can J Anaesth 1987 Nov; 34(6):601-5.
- 11. Dalens B, Tanguy A, Haberer JP. Lumbar epidural anesthesia for operative and postoperative pain relief in infants and young children. Anaesth Analg 1986 Oct; 65(10):1069-73.
- 12. Desparmet J, Meistelman C, Barre J, Saint-Maurice C. Continuous epidural infusion of bupivacaine for postoperative pain relief in children. Anesthesiology 1987 Jul; 67(1):108- 10.
- 13. Downing JW. Bupivacaine - A clinical assessment in lumbar extradural block. Brit J Anaesth 1969 May; 41(5):427-32.
- 14. Duthie AM, Wyman JB, Lewis GA. Bupivacaine in labour. Anaesthesia 1968 March; 23(1):20-26.
- 15. Forgas-Babjak A, McChesney J, Morison DH. The efficacy of buipivacaine 0.75 per cent as an epidural test dose. Can Anaesth Soc J 1980 Sept; 27(5):500-501.
- 16. Gills JP, Rudisill JE. Bupivacaine in cataract surgery. Ophthalmic Surgery. 1974 Winter; 5(4):67 70.
- 17. Hannington-Kiff JG. Treatment of intractable pain by bupivacaine nerve block. Lancet 1971 Dec 25; 2(7739):1392-4.
- 18. Hyman MD, Shnider SM. Maternal and neonatal blood concentrations of bupivacaine associated with obstetrical conduction anaesthesia. Anesthesiology 1971 Jan; 34(1):81-6.
- 19. Kennerdell JS, Rydze D, Robertson M. Comparison of retrobulbar marcaine and combined marcaine- carbocaine in ophthalmic surgery. Ann Ophthalmol 1976 Oct; 8(10):1236-40.
- 20. Libelius R, Sonesson B, Stamenović BA, Thesleff S. Denervation-like changes in skeletal muscle after treatment with a local anaesthetic. Marcaine J Anat 1970 Mar; 106(Pt 2):297-309.
- 21. Lund, PC, Cwik JC, Gannon RT. Extradural anesthesia: choice of local anaesthetic agents. Br J Anaesth 1975 Feb; 47 suppl:313-21.
- 22. Mather LE, Long GJ, Thomas J. Binding of bupivacaine to maternal and foetal plasma proteins. J Pharm Pharmacol 1971 May;23(5):359-65.
- 23. Mather LE, Long GJ, Thomas J. I.V. toxicity and clearance of bupivacaine in Man Clin Pharmacol Therap 1971 Nov-Dec;12(6):935-43.
- 24. McMorland GH, Biehl DR, Palahniuk RJ. Report of Canadian anaesthetists’ society ad hoc committee on cardiotoxicity of bupivacaine. May 1984.
- 25. Moore DC, Bridenbaugh LD, Bridenbaugh PO, Thompson GE. Bupivacaine HCl: A summary of investigational use in 3274 cases. Anesth Analg 1971 Sep-Oct; 50(5):856- 72.
- 26. Moore DC, Bridenbaugh LD, Bridenbaugh PO, Tucker GT. Caudal and epidural blocks with bupivacaine for childbirth. Report of 657 parturients. Obstet Gynec 1971 May; 37(5):667-76.
- 27. Moore DC, Bridenbaugh LD, Bridenbaugh PO, Tucker GT. Bupivacaine for peripheral nerve block. A comparison with mepivacaine, lidocaine, and tetracaine. Anesthesiology 1970 May; 32(5):460-3.
- 28. Moore DC, Bridenbaugh LD, Thompson GE, Balfour RI, Horton WG. Bupivacaine: A review of 11,080 cases. Anesth Analg 1978 Jan-Feb; 57(1):42-53.
- 29. Moore DC, Mather LE, Bridenbaugh LD, Balfour RI, Lysons DF, Horton WG. Arterial and venous plasma levels of bupivacaine following peripheral nerve blocks. Anesth Analg 1976 Nov-Dec; 55(6):763- 8.
- 30. Moore DC, Mather LE, Bridenbaugh LD, Thompson GE, Balfour RI, Lysons DF, et al. Bupivacaine (Marcaine*): An evaluation of its tissue and systemic toxicity in humans. Acta Anesth Scand 1977; 21(2):109-21.
- 31. Moore DC, Bridenbaugh LD, Thompson GE, Balfour RI, Horton WG. Factors determining dosages of amide-type local anesthetic drugs. Anesth 1977 Sep;47(3):263-8.
- 32. Noble AD, Craft IL, Bootes JA, Edwards PA, Thomas DJ, Mills KL. Continuous epidural analgesia using bupivacaine, A study of the foetus and newborn child. J Obstet Gyn Br CommonW 1971 Jun; 78(6):559- 63.
- 33. Reynolds F. Metabolism and excretion of bupivacaine in man: A comparison with mepivacaine. Br J Anaesth 1971 Jan; 43(1):33-7.
- 34. Solomon D, Navaie M, Stedje-Larsen E, Smith J, Provencher M. Glenohumeral Chondrolysis After Arthroscopy: A Systematic Review of Potential Contributors and Causal Pathways. J Arthr Rel Surg 2009; 25(11):1329-1342.
- 35. Shandling B, Steward DJ. Regional analgesia for postoperative pain in pediatric utpatient surgery. J Pediatr Surg. 1980 Aug; 15(4):477-80.
- 36. Simcock MJ. Bupivacaine for regional analgesia in labour. Med J Aust 1971;1:889-891.
- 37. Steel GC, Dawkins CJM. Extradural lumbar block with bupivacaine (Marcaine). Anaesthesia 1968; 23:14-19.
- 38. Thomas J, Long G, Moore G, Morgan D. Plasma protein binding and placental transfer of bupivacaine. Clin Pharmacol Ther 1976 Apr; 19(4):426-34.
- 39. Veering B, Burm AG, van Kleef JW, Hennis PJ, Spierdijk J. Epidural anesthesia with bupivacaine: Effects of age on neural blockade and pharmacokinetics. Anesth Analg 1987 Jul; 66(7):589-93.
- 40. Watt MJ, Ross DM, Atkinson RS. A double blind trial of bupivacaine and lignocaine, latency and duration in extradural blockade. Anaesthesia 1968 Jul; 23(3):331-7;23:331.
- 41. Widman B. Plasma concentration of local anaesthetic agents in regard to absorption, distribution and elimination, with special reference to bupivacaine. Br J Anaesth 1975 Feb; 47 suppl:231-6.
- 42. McNickle A, L’Heureux D, Provencher M, Romeo A, Cole B. Postsurgical Glenohumeral Arthritis in Young Adults. Am J Sports Med 2009; 37(9):1784-1791.
- 43. Product Monograph, Marcaine Spinal. Hospira Healthcare Corporation, April 6, 2011. Control No: 145715.
- 44. Product Monograph, Bupivacaine Heavy Injection BP. Auro Pharma Inc., December 11, 2017. Control No: 203187.
- 45. Product Monograph, Bupivacaine Hydrochloride in Dextrose Injection USP. SteriMax Inc., March 23, 2018, Control No: 212152.