


Product Monograph - Ciprofloxacin (Sanis Health, 750 mg)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | 250, 500, & 750 mg tablets | For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
CIPROFLOXACIN (Ciprofloxacin Tablets, USP) may be indicated for the treatment of patients with the following infections caused by susceptible strains of the indicated microorganisms:
Respiratory Tract Infections
Acute exacerbation of chronic bronchitis caused by: Haemophilus influenzae
Moraxella catarrhalis
Acute pneumonia caused by:
Enterobacter cloacae
Escherichia coli
Haemophilus influenzae
Klebsiella pneumoniae
Proteus mirabilis
Pseudomonas aeruginosa
Staphylococcus aureus
Acute sinusitis caused by:
Haemophilus influenzae
Moraxella catarrhalis
Due to the nature of the underlying conditions which usually predispose patients to pseudomonas infections of the respiratory tract, bacterial eradications may not be achieved in patients who display clinical improvement despite evidence of in vitro sensitivity. In patients requiring subsequent courses of therapy, CIPROFLOXACIN tablets should be used alternately with other antipseudomonal agents. Some strains of Pseudomonas aeruginosa may develop resistance during treatment. Therefore, susceptibility testing should be performed periodically during therapy to detect the emergence of bacterial resistance.
Urinary Tract Infections
Upper and lower urinary tract infections, such as complicated and uncomplicated cystitis, pyelonephritis, and pyelitis caused by:
Citrobacter diversus
Citrobacter freundii
Enterobacter cloacae
Escherichia coli
Klebsiella pneumoniae
Klebsiella oxytoca
Morganella morganii
Proteus mirabilis
Pseudomonas aeruginosa
Serratia marcescens
Staphylococcus aureus
Staphylococcus epidermidis
Staphylococcus saprophyticus
Streptococcus faecalis
Acute uncomplicated cystitis:
in females caused by Eschericia coli
Chronic Bacterial Prostatitis
Caused by:
Escherichia coli
Skin and Soft Tissue Infections
Caused by:
Enterobacter cloacae
Escherichia coli
Klebsiella pneumoniae
Proteus mirabilis
Proteus vulgaris
Pseudomonas aeruginosa
Staphylococcus aureus
Staphylococcus epidermidis
Streptococcus pyogenes
Bone and Joint Infections
Caused by:
Enterobacter cloacae
Pseudomonas aeruginosa
Serratia marcescens
Staphylococcus aureus
Infectious Diarrhea (when antibacterial therapy is indicated)
Caused by:
Campylobacter jejuni
Escherichia coli (enterotoxigenic strains)
Shigella dysenteriae
Shigella flexneri
Shigella sonnei
Meningococcal Carriers
Treatment of asymptomatic carriers of Neisseria meningitidis to eliminate meningococci from the nasopharynx. An MIC determination on the isolate from the index case should be performed as soon as possible. Ciprofloxacin is not indicated for the treatment of meningococcal meningitis.
Typhoid Fever (enteric fever)
Caused by:
Salmonella paratyphi
Salmonella typhi
Uncomplicated Gonorrhea
Cervical/urethral/rectal/pharyngeal infections caused by Neisseria gonorrhoea. Because co-infection with Chlamydia trachomatis is common, consideration should be given to treating presumptively with an additional regimen that is effective against C. trachomatis.
Appropriate culture and susceptibility tests should be performed prior to initiating treatment in order to isolate and identify organisms causing the infection and to determine their susceptibilities to ciprofloxacin. Therapy with CIPROFLOXACIN tablets may be initiated before results of these tests are known. However, modification of this treatment may be required once results become available or if there is no clinical improvement. Culture and susceptibility testing performed periodically during therapy will provide information on the possible
emergence of bacterial resistance. If anaerobic organisms are suspected to be contributing to the infection, appropriate therapy should be administered.
CONTRAINDICATIONS
CIPROFLOXACIN (Ciprofloxacin tablets, USP) is contraindicated in patients who have shown hypersensitivity to ciprofloxacin, or other quinolone antibacterial agents or any of the excipients.
Concurrent administration of ciprofloxacin and tizanidine is contraindicated since it may result in an undesirable increase in serum tizanidine concentrations. This can be associated with clinically relevant tizanidine-induced side effects (hypotension, somnolence, drowsiness).
WARNINGS AND PRECAUTIONS
General
The safety and efficacy of CIPROFLOXACIN (Ciprofloxacin tablets, USP) in children, adolescents (under the age of 18 years), pregnant women and nursing women have not been established. (See Special Populations below: Pregnant Women, Nursing Women, and Pediatrics)
Ability to Drive and Operate Machinery: Fluoroquinolones including ciprofloxacin may result in an impairment of the patient’s ability to drive or operate machinery due to CNS reactions. This applies particularly in combination with alcohol (see ADVERSE REACTIONS).
Streptococcus pneumonia Infections: Ciprofloxacin is not recommended for treatment of pneumococcal infections due to inadequate efficacy against Streptococcus pneumoniae.
Cardiovascular
Cardiac Disorders: Ciprofloxacin has been shown to prolong the QT interval of the electrocardiogram in some patients. In general, elderly patients may be more susceptible to drug-associated effects on the QT interval. Precaution should be taken when using ciprofloxacin with concomitant drugs that can result in prolongation of the QT interval (eg, class IA or III antiarrhythmics) or in patients with risk factors for torsade de pointes (eg, known QT prolongation, uncorrected hypokalemia) (see DRUG INTERACTIONS and ADVERSE REACTIONS).
Cytochrome P450
Ciprofloxacin is known to be a moderate inhibitor of the CYP450 1A2 enzymes. Care should be taken when other drugs are administered concomitantly which are metabolized via the same enzymatic pathway (e.g., theophylline, methylxanthines, caffeine, duloxetine, clozapine).
Increased plasma concentrations associated with drug specific side effects may be observed due to inhibition of their metabolic clearance by ciprofloxacin (see CONTRAINDICATIONS and DRUG INTERACTIONS).
Endocrine and Metabolism
Disturbances of Blood Glucose: Disturbances of blood glucose, including symptomatic hyper- and hypoglycemia, have been reported with the use of quinolones, including ciprofloxacin (see ADVERSE REACTIONS).
Gastrointestinal
Clostridium difficile-associated disease: Clostridium difficile-associated disease (CDAD) has been reported with the use of many antibacterial agents, including ciprofloxacin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and many permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against C. difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against C. difficile. Drugs that inhibit peristalsis may delay clearance of C. difficile and its toxins, and therefore should not be used in the treatment of CDAD. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic
In preliminary studies in patients with stable chronic liver cirrhosis (with mild to moderate hepatic impairment), no significant changes in ciprofloxacin pharmacokinetics were observed. The kinetics of ciprofloxacin in patients with acute hepatic insufficiency and stable chronic cirrhosis (with severe hepatic impairment), however, have not been fully elucidated. An increased incidence of nausea, vomiting, headache and diarrhea were observed in this patient population (see DETAILED PHARMACOLOGY, Human Pharmacology).
Musculoskeletal
Myasthenia Gravis: Fluoroquinolones, including ciprofloxacin, have neuromuscular blocking activity and may exacerbate muscle weakness in persons with myasthenia gravis. Postmarketing serious adverse events, including deaths and requirement for ventilatory support, have been associated with fluoroquinolone use in persons with myasthenia gravis. Avoid ciprofloxacin in patients with a known history of myasthenia gravis (see ADVERSE REACTIONS).
Tendinitis: Rupture of the shoulder, hand and Achilles tendons that required surgical repair or resulted in prolonged disability have been reported in patients receiving quinolones, including ciprofloxacin (see ADVERSE REACTIONS). Ciprofloxacin should be discontinued if the patient experiences pain, inflammation, or rupture of a tendon. Patients should rest and refrain from exercise until the diagnosis of tendinitis or tendon rupture has been confidently excluded. The risk of developing fluoroquinolone-associated tendinitis and tendon rupture is further increased in older patients usually over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart, or lung transplants. Factors, in addition to age and corticosteroid use, that may independently increase the risk of tendon rupture include strenuous physical activity, renal failure, and previous tendon disorders such as rheumatoid arthritis. Tendinitis and tendon rupture have also occurred in patients taking fluoroquinolones who do not have the above risk factors. Tendon rupture can occur during or after completion of therapy; cases occurring up to several months after completion of therapy have been reported. Ciprofloxacin should be discontinued if the patient experiences pain, swelling, inflammation, or rupture of a tendon. Patients should be advised to rest at the first sign of tendinitis or tendon rupture, and to contact their healthcare provider regarding changing to a non-quinolone antimicrobial drug.
Ciprofloxacin should not be used in patients with a history of tendon disease/disorder related to previous quinolone treatment.
Neurologic
CNS and Psychiatric Effects: Seizures and toxic psychoses may occur with quinolone therapy. Convulsions, increased intracranial pressure (including pseudotumor cerebri), and toxic psychoses have been reported in patients receiving quinolones, including ciprofloxacin. Ciprofloxacin may also cause central nervous system (CNS) stimulation which may lead to tremors, restlessness, lightheadedness, confusion, hallucinations, depression, nervousness, agitation, insomnia, anxiety, paranoia, nightmares and rarely, suicidal thoughts or acts. In rare cases, depression or psychosis can progress to self-endangering behaviour. These reactions may occur following the first dose. If these reactions occur in patients receiving ciprofloxacin, the drug should be discontinued and appropriate measures instituted. Ciprofloxacin should be used with caution in patients with known or suspected CNS disorders which may predispose to seizures or lower the seizure threshold (see ADVERSE REACTIONS).
Peripheral Neuropathy: Rare cases of sensory or sensorimotor axonal polyneuropathy affecting small and/or large axons resulting in paresthesias, hypoesthesias, dysesthesias and weakness
have been reported in patients receiving quinolones, including ciprofloxacin (see ADVERSE REACTIONS).
Renal
Crystalluria related to ciprofloxacin has been reported only rarely in man because human urine is usually acidic. Crystals have been observed in the urine of laboratory animals, usually from alkaline urine. Patients receiving ciprofloxacin should be well hydrated and alkalinity of the urine should be avoided. The recommended daily dose should not be exceeded.
Since ciprofloxacin is eliminated primarily by the kidney, CIPROFLOXACIN tablets should be used with caution and at a reduced dosage in patients with impaired renal function (see DOSAGE AND ADMINISTRATION and DETAILED PHARMACOLOGY, Human Pharmacology).
Sensitivity/Resistance
Hypersensitivity: Serious hypersensitivity and/or anaphylactic reactions have been reported in patients receiving quinolone therapy, including ciprofloxacin (see ADVERSE REACTIONS). These reactions may occur within the first 30 minutes following the first dose and may require epinephrine and other emergency measures. Some reactions have been accompanied by cardiovascular collapse, hypotension/shock, seizure, loss of consciousness, tingling, angioedema (including tongue, laryngeal, throat or facial edema/swelling), airway obstruction (including bronchospasm, shortness of breath and acute respiratory distress), dyspnea, urticaria, itching and other serious skin reactions.
Ciprofloxacin should be discontinued at the first appearance of a skin rash or any other sign of hypersensitivity. Serious acute hypersensitivity reactions may require treatment with epinephrine and other resuscitative measures, including oxygen, intravenous fluids, antihistamines, corticosteroids, pressor amines and airway management, as clinically indicated.
Serious and sometimes fatal events, some due to hypersensitivity and some due to uncertain etiology, have been reported in patients receiving therapy with all antibiotics. These events may be severe and generally occur following the administration of multiple doses. Clinical manifestations may include one or more of the following: fever, rash or severe dermatologic reactions (e.g., toxic epidermal necrolysis, Stevens-Johnson Syndrome), vasculitis, arthralgia, myalgia, serum sickness, allergic pneumonitis, interstitial nephritis, acute renal insufficiency or failure, hepatitis, jaundice, acute hepatic necrosis or failure, hepatic necrosis with fatal outcome, anemia including hemolytic and aplastic, thrombocytopenia including thrombotic thrombocytopenic purpura, leukopenia, agranulocytosis, pancytopenia, and/or other hematologic abnormalities.
Ciprofloxacin has been shown to produce photosensitivity reactions. Patients taking ciprofloxacin should avoid direct exposure to excessive sunlight or UV-light. Therapy should be discontinued if photosensitization (i.e., sunburn-like skin reactions) occurs.
Prolonged use of CIPROFLOXACIN Tablets may result in the overgrowth of nonsusceptible organisms. Careful observation of the patient is therefore essential, and if superinfection should occur during therapy, appropriate measures should be taken.
Skin
Phototoxicity: Moderate to severe phototoxicity reactions have been observed in patients exposed to direct sunlight or ultraviolet light while receiving drugs in this class. Excessive exposure to sunlight or ultraviolet light should be avoided. Therapy should be discontinued if phototoxicity occurs.
Special Populations
Pregnant Women: The safety of ciprofloxacin hydrochloride in pregnancy has not yet been established. CIPROFLOXACIN Tablets should not be used in pregnant women unless the likely benefits outweigh the possible risk to the fetus (see WARNINGS AND PRECAUTIONS, General above). Ciprofloxacin hydrochloride has been shown to be non-embryotoxic and non-teratogenic in animal studies.
Nursing Women: Ciprofloxacin is excreted in human milk. Because of the potential for serious adverse reactions in infants nursing from women taking ciprofloxacin, a decision should be made to discontinue nursing or to discontinue the administration of CIPROFLOXACIN, taking into account the importance of the drug to the mother and the possible risk to the infant (see WARNINGS AND PRECAUTIONS, General above)
Pediatrics: The safety and efficacy of ciprofloxacin in the pediatric population less than 18 years of age have not been established. Quinolones, including ciprofloxacin, cause arthropathy and osteochondrosis in juvenile animals of several species (see WARNINGS AND PRECAUTIONS and TOXICOLOGY). Damage to juvenile weight-bearing joints and lameness were observed both in rat and dog studies but not in weaned piglets (see TOXICOLOGY). Histopathological examination of the weight-bearing joints in immature dogs revealed permanent lesions of the cartilage.
Geriatrics: Ciprofloxacin is substantially excreted by the kidney, and the risk of adverse reactions may be greater in patients with impaired renal function (see DETAILED PHARMACOLOGY, Human Pharmacology).
Theophylline
SERIOUS AND FATAL REACTIONS HAVE BEEN REPORTED IN PATIENTS RECEIVING CONCURRENT ADMINISTRATION OF CIPROFLOXACIN AND THEOPHYLLINE. These reactions include cardiac arrest, seizure, status epilepticus and respiratory failure. Similar serious adverse events have been noted with administration of theophylline alone; however, the possibility that ciprofloxacin may potentiate these reactions
cannot be eliminated. If concomitant use cannot be avoided, the plasma levels of theophylline should be monitored and appropriate dosage adjustments should be made.
Monitoring and Laboratory Tests
Interaction with Tests: Ciprofloxacin in vitro potency may interfere with the Mycobacterium spp. culture test by suppression of mycobacterial growth, causing false negative results in specimens from patients currently taking ciprofloxacin.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Ciprofloxacin hydrochloride tablets are generally well tolerated. During worldwide clinical investigation (1991), 16,580 courses of ciprofloxacin treatment were evaluated for drug safety. The incidence of adverse reactions was 8.0%. In orally treated patients enrolled in clinical trials, the most frequently reported events, possibly, probably drug-related were: nausea (1.3%), and diarrhea (1.0%).
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Events possibly, probably drug-related occurring at a frequency of less than 1% with ciprofloxacin treatment during clinical trials and subsequent post-marketing surveillance are as follows:
Body as a Whole: back pain, chest pain, pain, pain in extremities, moniliasis.
Cardiovascular System: palpitation, phlebitis, tachycardia, thrombophlebitis. The following has been reported rarely ≥ 0.01% <0.1%): hypotension. The following have been reported very rarely (<0.01%): angina pectoris, atrial fibrillation, cardiac arrest, cerebrovascular disorder, electrocardiogram abnormality, hot flashes, hypertension, kidney vasculitis, myocardial infarct, pericarditis, pulmonary embolus, substernal chest pain, syncope (fainting), vasodilation (hot flashes).
Digestive: abdominal pain, anorexia, dry mouth, dyspepsia, dysphagia, enlarged abdomen, flatulence, gastrointestinal moniliasis, jaundice, stomatitis, vomiting, abnormal liver function test. The following have been reported rarely: moniliasis (oral), cholestatic jaundice, and
pseudomembranous colitis. The following have been reported very rarely: constipation, esophagitis, gastrointestinal hemorrhage, glossitis, hepatomegaly, ileus, increased appetite, intestinal perforation, life-threatening pseudomembranous colitis with possible fatal outcome, liver damage, melena, pancreatitis, tenesmus, tooth discoloration, toxic megacolon, ulcerative stomatitis.
Hemic and Lymphatic: agranulocytosis, anaemia, eosinophilia, granulocytopenia, leukocytopenia, leukocytosis, pancytopenia. The following have been reported very rarely: altered prothrombin levels, haemolytic anaemia, marrow depression (life threatening), pancytopenia (life threatening), thrombocytopenia, thrombocytosis.
Hypersensitivity: rash. The following have been reported rarely: allergic reaction, anaphylactic/anaphylactoid reactions including facial, vascular and laryngeal edema, drug fever, haemorrhagic bullae and small nodules (papules) with crust formation showing vascular involvement (vasculitis), hepatitis, interstitial nephritis, petechiae (punctuate skin hemorrhages), pruritus, serum sickness-like reaction, Stevens-Johnson syndrome (potentially life-threatening) (see WARNINGS AND PRECAUTIONS). The following have been reported very rarely: shock (anaphylactic; life-threatening), pruritic rash, erythema multiforme (minor), erythema nodosum, major liver disorders including hepatic necrosis, (very rarely progressing to life threatening hepatic failures), epidermal necrolysis (Lyell Syndrome, potentially life-threatening).
Metabolic and Nutritional Disorder: creatinine increased. The following have been reported rarely: edema (face) and hyperglycemia (see WARNINGS AND PRECAUTIONS).
Musculoskeletal: The following have been reported rarely in patients for all ages: achiness, arthralgia (joint pain), joint disorder (joint swelling), pain in the extremities, partial or completed tendon rupture (shoulder, hand or Achilles tendon), tendinitis (predominantly achillotendinitis), myalgia (muscular pain). The following have been reported very rarely: myasthenia (exacerbation of symptoms of myasthensia gravis) (see WARNINGS AND PRECAUTIONS).
Nervous System: agitation, confusion, convulsion, dizziness, hallucinations, headache, hypesthesia, increased sweating, insomnia, somnolence, tremor (trembling). The following has been reported rarely: paresthesia (peripheral paralgesia) (see WARNINGS AND PRECAUTIONS). The following have been reported very rarely: abnormal dreams (nightmares), anxiety, apathy, ataxia, depersonalization, depression, diplopia, hemiplegia, hyperesthesia, hypertonia, increase of intracranial pressure, meningism, migraine, nervousness, neuritis, paresthesia, polyneuritis, sleep disorder, twitching, grand mal convulsions, abnormal (unsteady) gait, psychosis, intracranial hypertension. In some instances these reactions occurred after the first administration of ciprofloxacin. In these instances, ciprofloxacin has to be discontinued and the doctor should be informed immediately.
Other: The following have been reported rarely: asthenia (general feeling of weakness, tiredness), death.
Respiratory System: dyspnea. The following have been reported very rarely: hiccup, hyperventilation, increased cough, larynx edema, lung edema, lung hemorrhage, pharyngitis, stridor, voice alteration.
Skin/Appendages: pruritus, rash, maculopapular rash. The following has been reported rarely: photosensitivity reaction. The following have been reported very rarely: alopecia, angioedema, fixed eruption, photosensitive dermatitis, petechia, urticaria.
Special Senses: abnormal vision (visual disturbances), taste perversion, tinnitus. The following have been reported rarely: transitory deafness (especially at higher frequencies), taste loss (impaired taste). The following have been reported very rarely: chromatopsia, colour blindness, conjunctivitis, corneal opacity, diplopia, ear pain, eye pain, parosmia (impaired smell), anosmia (usually reversible on discontinuation).
Urogenital System: albuminuria, hematuria. The following have been reported rarely: abnormal kidney function, acute kidney failure, dysuria, leukorrhea, nephritis interstitial, urinary retention, vaginitis, vaginal moniliasis.
Laboratory Values: increased alkaline phosphatase, ALT increased, AST increased, BUN (urea) increased, cholestatic parameters increased, Gamma - GT increased, lactic dehydrogenase increased, NPN increased, transaminases increased, decreased albuminuria, bilirubinemia, creatinine clearance decreased, hypercholesteremia, hyperuricemia, increased sedimentation rate. The following have been reported rarely: acidosis, increased amylase, crystalluria, electrolyte abnormality, haematuria, hypercalcemia, hypocalcemia and lipase increased.
Most of the adverse events reported were described as only mild or moderate in severity.
The following additional adverse events, in alphabetical order, regardless of incidence or relationship to drug, have been reported during clinical trials and from worldwide post-marketing experience in patients given ciprofloxacin (includes all formulations, all dosages, all drug-therapy durations, and in all indications): arrhythmia, atrial flutter, bleeding diathesis, bronchospasm, C. difficile associated diarrhea, candiduria, cardiac murmur, cardiopulmonary arrest, cardiovascular collapse, cerebral thrombosis, chills, delirium, drowsiness, dysphasia, edema (conjunctivae, hands, lips, lower extremities, neck), epistaxis, exfoliative dermatitis, fever, gastrointestinal bleeding, gout (flare up), gynecomastia, hearing loss, hemoptysis, hemorrhagic cystitis, hyperpigmentation, joint stiffness, lightheadedness, lymphadenopathy, manic reaction, myoclonus, nystagmus, pain (arm, breast, epigastric, foot, jaw, neck, oral mucosa), paranoia, peripheral neuropathy, phobia, pleural effusion, polyneuropathy, polyuria, postural hypotension, pulmonary embolism, purpura, QT prolongation, renal calculi, respiratory
arrest, respiratory distress, restlessness, rhabdomyolysis, torsades de pointes, toxic psychosis, unresponsiveness, urethral bleeding, urination (frequent), ventricular ectopy, ventricular fibrillation, ventricular tachycardia, vesicles, visual acuity (decreased) and visual disturbances (flashing lights, change in colour perception, overbrightness of lights).
DRUG INTERACTIONS
Drug-Drug Interactions
Class IA or III Antiarrhythmics: Precaution should be taken when using ciprofloxacin together with class IA or III antiarrhythmics as ciprofloxacin may have an additive effect on the QT interval (see WARNINGS AND PRECAUTIONS).
Clozapine: Following concomitant administration of 250 mg ciprofloxacin for 7 days, serum concentrations of clozapine and n-desmethylclozapine were increased by 29% and 31%, respectively (see WARNINGS AND PRECAUTIONS).
Cyclosporine: Some quinolones, including ciprofloxacin, have been associated with transient increases in serum creatinine levels in patients who are concomitantly receiving cyclosporine.
Duloxetine: In clinical studies it was demonstrated that concomitant use of duloxetine with strong inhibitors of the CYP450 1A2 isozyme such as fluvoxamine, may result in an increase of AUC and Cmax of duloxetine. Although no clinical data are available on a possible interaction with ciprofloxacin, similar effects can be expected upon concomitant administration.
Ferrous Sulfate: Oral ferrous sulfate at therapeutic doses decreases the bioavailability of oral ciprofloxacin, therefore concomitant therapy is not advised.
Glyburide: In particular cases, concurrent administration of ciprofloxacin and glyburide can intensify the action of glyburide (hypoglycemia).
Histamine H2-receptor Antagonists: Histamine H2-receptor antagonists appear to have no significant effect on the bioavailability of ciprofloxacin.
Lidocaine: It was demonstrated in healthy subjects that concomitant use of lidocaine with ciprofloxacin, a moderate inhibitor of CYP450 1A2 isozyme, reduces clearance of intravenous lidocaine by 22%. Ciprofloxacin may increase the systemic toxicity of lidocaine.
Methotrexate: Renal tubular transport of methotrexate may be inhibited by concomitant administration of ciprofloxacin, potentially leading to increased plasma levels of methotrexate. This might increase the risk of methotrexate associated toxic reactions. Therefore, patients under methotrexate therapy should be carefully monitored when concomitant ciprofloxacin therapy is indicated.
Metoclopramide: Metoclopramide accelerates the absorption of ciprofloxacin (oral), resulting in a shorter time to reach maximum plasma concentrations. No effect was seen on the bioavailability of ciprofloxacin.
Multivalent Cations: Concurrent administration of a quinolone, including ciprofloxacin, with multivalent cation-containing products such as magnesium/aluminum antacids, polymeric phosphate binders such as sevelamer, lanthanum carbonate, sucralfate, Videx® (didanosine) chewable/buffered tablets or pediatric powder, mineral supplements or products containing calcium, iron, or zinc may substantially interfere with the absorption of the quinolone, resulting in serum and urine levels considerably lower than desired. Ciprofloxacin should be administered at least 2 hours before or 6 hours after these preparations.
NSAID: Concomitant administration of a nonsteroidal anti-inflammatory drug (fenbufen) with a quinolone (enoxacin) has been reported to increase the risk of CNS stimulation and convulsive seizures.
Probenecid: Probenecid blocks renal tubular secretion of ciprofloxacin and has been shown to produce an increase in the level of ciprofloxacin in the serum.
Ropinirole: In a clinical study it was shown that concomitant use of ropinirole with ciprofloxacin, a medium inhibitor of the CYP450 1A2 isozyme, resulted in increases in the Cmax and AUC of ropinirole of 60% and 84%, respectively. Ciprofloxacin may increase the systemic toxicity of ropinirole.
Sildenafil: Cmax and AUC of sildenafil were increased approximately two-fold in healthy subjects after an oral dose of 50 mg was given concomitantly with 500 mg ciprofloxacin. Therefore, caution should be used when prescribing ciprofloxacin concomitantly with sildenafil, taking into consideration the risks and the benefits.
Theophylline: Concurrent administration of ciprofloxacin with theophylline may lead to elevated serum concentrations of theophylline and prolongation of its elimination half-life. This may result in increased risk of theophylline-related adverse reactions. If concomitant use cannot be avoided, serum levels of theophylline should be monitored and dosage adjustments made as appropriate.
Tizanidine: In a clinical study in healthy subjects there was an increase in tizanidine serum concentrations (Cmax increase: 7-fold, range: 4 to 21-fold; AUC increase: 10-fold, range: 6 to 24-fold) when given concomitantly with ciprofloxacin. Associated with the increased serum concentrations was a potentiated hypotensive and sedative effect. Tizanidine must not be administered together with ciprofloxacin. (See CONTRAINDICATIONS)
Vitamin K Antagonists: Simultaneous administration of ciprofloxacin with a vitamin K antagonist may augment its anticoagulant effects. The risk may vary with the underlying infection, age, and general status of the patient so that the contribution of ciprofloxacin to the increase in INR (international normalized ratio) is difficult to assess. The INR should be monitored frequently during and shortly after co-administration of ciprofloxacin with a vitamin K antagonist (e.g. warfarin and acenocoumarol).
Drug-Food Interactions
Caffeine and Other Xanthine Derivatives: Caffeine has been shown to interfere with the metabolism and pharmacokinetics of ciprofloxacin. Excessive caffeine intake should be avoided.
Upon concurrent administration of ciprofloxacin and pentoxifylline (oxpentifylline)-containing products, raised serum concentrations of this xanthine derivative were reported.
Food and Dairy Products: Although, ciprofloxacin may be taken with meals that include milk, simultaneous administration with dairy products alone, or with calcium-fortified products should be avoided, since decreased absorption is possible. It is recommended that ciprofloxacin be administered at least 2 hours before or 2 hours after substantial calcium intake (>800 mg) (see DOSAGE AND ADMINISTRATION).
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The determination of dosage for any particular patient must take into consideration the severity and nature of the infection, the susceptibility of the causative organism, the integrity of the patient's host-defence mechanisms, and the status of renal function.
Recommended Dose and Dosage Adjustment
Adults
The recommended dosages of CIPROFLOXACIN tablets are:
Table 1: Recommended Dosages for CIPROFLOXACIN
| Location of Infection | Type/Severity | Unit Dose | Frequency | Daily Dose |
| Location of Infection | Type/Severity | Unit Dose | Frequency | Daily Dose |
| Urinary Tract | Mild/Moderate | 250 mg | q12h | 500 mg |
| Severe/Complicated | 500 mg | q12h | 1000 mg | |
| Chronic Bacterial Prostatitis | Asymptomatic/Mild/Moderate | 500 mg | q12h | 1000 mg |
| Respiratory Tract Bone & Joint Skin & Soft Tissue | Mild/Moderate | 500 mg | q12h | 1000 mg |
| Severe*/Complicated | 750 mg | q12h | 1500 mg | |
| Infectious Diarrhea | Mild/Moderate/Severe | 500 mg | q12h | 1000 mg |
Urogenital and Extragenital Gonorrhea | Uncomplicated | 500 mg | Once | 500 mg |
| Typhoid Fever | Mild/Moderate | 500 mg | q12h | 1000 mg |
| Neisseria meningitidis Nasopharyngeal colonization | Carrier State | 750 mg | Once | 750 mg |
| Acute Sinusitis | Moderate | 500 mg | q12h | 1000mg |
* e.g., hospital-acquired pneumonia, osteomyelitis
Depending on the severity of the infections, as well as the clinical and bacteriological responses, the average treatment period should be approximately 7 to 14 days. Generally, treatment should last 3 days beyond the disappearance of clinical symptoms or until cultures are sterile. Patients with osteomyelitis may require treatment for a minimum of 6 to 8 weeks and up to 3 months. With acute cystitis in females a 3 to 5 day treatment may be sufficient. With infectious diarrhea a five-day treatment may be sufficient. Typhoid fever should be treated for 14 days. Acute sinusitis should be treated for 10 days with 500 mg q 12h. Chronic bacterial prostatitis should be treated for 28 days with 500 mg q 12h.
Impaired Renal Function
Ciprofloxacin is eliminated primarily by renal excretion. However, the drug is also metabolized and partially cleared through the biliary system of the liver and through the intestine. (See DETAILED PHARMACOLOGY, Human Pharmacology). This alternate pathway of drug elimination appears to compensate for the reduced renal excretion of patients with renal impairment. Nonetheless, some modification of dosage is recommended, particularly for patients with severe renal dysfunction. The following table provides a guideline for dosage adjustment of ciprofloxacin hydrochloride tablets. However, monitoring of serum drug levels provides the most reliable basis for dosage adjustments.
Table 2: Maximum Daily Dose with Stated Creatinine Clearance or Serum Creatinine
Creatinine Clearance mL/min/1.73m2 | Maximum Daily Dose Oral | Serum Creatinine Concentration mg/100mL |
| 31-60 | 1000 mg | 1.4-1.9 |
| ≤ 30 | 500 mg | ≥ 2.0 |
Maximum daily doses are not to be exceeded when either creatinine clearance or serum creatinine are in the ranges stated.
Hemodialysis
Only a small amount of ciprofloxacin (< l0%) is removed from the body after hemodialysis or peritoneal dialysis. For hemodialysis patients, please follow dosing recommendations as described in Table 2. On dialysis days, the dose should be administered after dialysis.
When only the serum creatinine concentration is available, the following formula (based on sex, weight and age of the patient) may be used to convert this value into creatinine clearance. The serum creatinine should represent a steady state of renal function:
Creatinine Clearance mL/sec =
Males: Weight (kg) x (140 - age)
49 x serum creatinine (µmol/L)
Females: 0.85 x the above value
In traditional units mL/min=
Males: Weight (kg) x (140 – age)
72 x serum creatinine (mg/100 mL)
Females: 0.85 x the above value
Impaired Hepatic Function
No dosage adjustment is required.
Pediatric Use
The safety and efficacy of ciprofloxacin hydrochloride tablets in individuals less than 18 years of age has not been established. CIPROFLOXACIN should not be used in pediatric patients and adolescents (see WARNINGS AND PRECAUTIONS).
Administration
CIPROFLOXACIN (Ciprofloxacin tablets, USP) may be taken before or after meals. Absorption is faster on an empty stomach. Patients should be advised to drink fluids liberally
and avoid taking dairy products or antacids containing magnesium or aluminum.
Ciprofloxacin should be administered at least 2 hours before or 6 hours after antacids and mineral supplements containing magnesium or aluminum, as well as sucralfate, Videx® (didanosine) chewable/buffered tablets or pediatric powder, metal cations such as iron, and multivitamin preparations with zinc. (See DRUG INTERACTIONS)
Although ciprofloxacin may be taken with meals that include milk, simultaneous administration with dairy products alone, or with calcium-fortified products should be avoided, since decreased absorption is possible. It is recommended that ciprofloxacin be administered at least 2 hours before or 2 hours after substantial calcium intake (>800 mg). (See DRUG INTERACTIONS)
OVERDOSAGE
In the event of acute, excessive oral overdosage, reversible renal toxicity, arthralgia, myalgia and CNS symptoms have been reported. Therefore, apart from routine emergency measures, it is recommended to monitor renal function and to administer magnesium- or calcium-containing antacids which reduce the absorption of ciprofloxacin and to maintain adequate hydration. Based on information obtained from subjects with chronic renal failure, only a small amount of ciprofloxacin (< 10%) is removed from the body after hemodialysis or peritoneal dialysis.
The administration of activated charcoal as soon as possible after oral overdose may prevent excessive increase of systemic ciprofloxacin exposure.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ciprofloxacin, a synthetic fluoroquinolone, has in vitro activity against a wide range of gram-negative and gram-positive microorganisms. Its bactericidal action is achieved through inhibition of topoisomerase II (DNA gyrase) and topoisomerase IV (both Type II topoisomerases), which are required for bacterial DNA replication, transcription, repair, and recombination.
Ciprofloxacin retained some of its bactericidal activity after inhibition of RNA and protein synthesis by rifampin and chloramphenicol, respectively. These observations suggest ciprofloxacin may possess two bactericidal mechanisms, one mechanism resulting from the For management of a suspected drug overdose, contact your regional Poison Control Centre immediately.
inhibition of DNA gyrase and a second mechanism which may be independent of RNA and protein synthesis.
The mechanism of action of fluoroquinolones, including ciprofloxacin, is different from that of penicillins, cephalosporins, aminoglycosides, macrolides, and tetracyclines. Therefore, microorganisms resistant to these classes of drugs may be susceptible to ciprofloxacin. Conversely, microorganisms resistant to fluoroquinolones may be susceptible to these other classes of antimicrobial agents (see MICROBIOLOGY). There is no cross-resistance between ciprofloxacin and the mentioned classes of antibiotics.
Pharmacokinetics
(See DETAILED PHARMACOLOGY, Human Pharmacology)
Absorption: Following oral administration of single doses of 250 mg, 500 mg, and 750 mg of ciprofloxacin tablets, ciprofloxacin is absorbed rapidly and extensively mainly from the small intestine, reaching maximum serum concentrations 1-2 hours later.
The absolute bioavailability is approximately 70-80%. Maximum serum concentrations (Cmax) and total areas under serum concentration vs. time curves (AUC) increased in proportion to dose.
Distribution: The protein binding of ciprofloxacin is low (20-30%), and the substance is present in plasma largely in a non-ionized form. Ciprofloxacin can diffuse freely into the extravascular space. The large steady-state volume of distribution of 2-3 L/kg body weight shows that ciprofloxacin penetrates in tissues resulting in concentrations which clearly exceed the corresponding serum levels.
Metabolism: Small concentrations of four metabolites have been reported. They were identified as desethyleneciprofloxacin (M1), sulphociprofloxacin (M2), oxociprofloxacin (M3) and formylciprofloxacin (M4). M1 to M3 display antibacterial activity comparable to or inferior to that of nalidixic acid. M4, with the smallest quantity, is largely equivalent to norfloxacin in its antimicrobial activity.
Excretion: Ciprofloxacin is largely excreted unchanged both renally and to a smaller extent non-renally. Renal clearance is between 0.18 to 0.3 L/h/kg and the total body clearance between 0.48 to 0.60 L/h/kg. Ciprofloxacin undergoes both glomerular filtration and tubular secretion.
Non-renal clearance of ciprofloxacin is mainly due to active transintestinal secretion as well as metabolization. 1% of the dose is excreted via the biliary route. Ciprofloxacin is present in the bile in high concentrations.
CR 250 STORAGE AND STABILITY
Store between 15°C and 30°C
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability of Dosage Forms :
CIPROFLOXACIN (Ciprofloxacin Tablets,
USP) 250 mg
Each white to off-white round, biconvex, film-coated tablet, embossed “ ” on one side and “>” on the other side, contains ciprofloxacin hydrochloride equivalent to 250 mg ciprofloxacin.
HDPE bottles of 100’s
CIPROFLOXACIN (Ciprofloxacin Tablets,
USP) 500 mg
Each white to off-white, capsule shaped, biconvex, film-coated tablet, embossed “CR 500” on one side and “>” on the other side, contains ciprofloxacin hydrochloride equivalent to 500 mg ciprofloxacin.
HDPE bottles of 100’s
CIPROFLOXACIN (Ciprofloxacin Tablets,
USP) 750 mg
Each white to off-white, capsule shaped, bioconvex, film-coated tablet, embossed “CR 750” on one side and “>” on the other side, contains ciprofloxacin hydrochloride equivalent to 750 mg ciprofloxacin.
HDPE bottles of 50’s
Composition:
Ciprofloxacin Hydrochloride, colloidal silicon dioxide, corn starch, crospovidone, magnesium stearate, microcrystalline cellulose, polyethyleneglycol, polyvinyl alcohol, pregelatinized starch, talc and titanium dioxide
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ciprofloxacin hydrochloride, USP
Chemical name: 1-cyclopropyl-6-fluoro-1,4-dihydro-4-oxo-7-(1-piperzinyl)-3-quinolinecarboxylic acid hydrochloride monohydrate
Molecular formula and molecular mass: C17H18FN3O3HCl H2O ; 385.8
Structural formula:
N
F C
C
O
CH
N
HN
COOH
HCl H2O . .
Physicochemical properties: Ciprofloxacin hydrochloride is a pale yellow crystalline powder. Sparingly soluble in water, slightly soluble in methanol, very slightly soluble in ethanol, practically insoluble in acetone, in ethyl acetate, and in methylene chloride.
pH solubility profile: pH Solubility
1 12 mg/mL
2 36 mg/mL
3 39 mg/mL
4 42 mg/mL 5 36 mg/mL 6 38 mg/mL 7 38 mg/mL 8 38 mg/mL
pH and pKa values: pH of a 2.5% solution in water is 3.0-4.5 The pKa1 is 6.1 and the pKa2 is 8.7
Melting Point: 318 – 320 °C
CLINICAL TRIALS
Comparative Bioavailability Studies
A comparative bioavailability study under fasting conditions was performed on CIPROFLOXACIN against the Canadian Reference Product, Cipro® (Bayer Inc.). The study was a blinded, single-dose, randomized, two-way cross-over, bioequivalence study on two formulations of the 750 mg ciprofloxacin tablets. The pharmacokinetic data are presented in the following table.
Two-way, Crossover Single Dose (1 x 750 mg) Fasted Study from Measured Data on Ciprofloxacin
Geometric Mean Arithmetic Mean (CV %)
| Parameter | Test† | Reference* | % Ratio of Geometric Means |
AUCT (ng.h/mL) | 16020 16293 (19) | 15219 15437 (17) | 105 |
AUCI (ng.h/mL) | 16196 16468 (19) | 15390 15607 (17) | 105 |
CMAX (ng/mL) | 2930 2982 (20) | 2851 2877 (14) | 103 |
| 1TMAX (h) | 1.33 (31) | 1.34 (34) | |
| 1T½ (h) | 5.71 (11) | 5.77 (12) |
† CIPROFLOXACIN 750 mg (Sanis Health Inc., Canada)
* Cipro® 750 mg manufactured by Bayer Inc., Canada. Purchased in Canada.
1 expressed as arithmetic mean (CV%) only
DETAILED PHARMACOLOGY
Animal Pharmacology
Effects on Histamine Release
Ciprofloxacin was administered intravenously to 9 anaesthetized dogs (initially with thiopental sodium at 25 mg/kg i.v., followed by continuous infusion of a mixture of fentanyl 0.04 mg/kg/hr and dehydrobenzperidol 0.25 mg/kg/hr) at a single dose of 3, 10 or 30 mg/kg. Ciprofloxacin treatment resulted in circulatory changes similar to those caused by histamine release. These
were reductions in blood pressure, cardiac output and maximum rate of pressure increase in the left ventricle (dp/dtmax), and increase in heart rate. This histamine-liberating effect was counteracted by the simultaneous intravenous administration of 0.01 mg/kg pyrilamine maleate. No signs of histamine liberation were observed on conscious animals.
In vitro experiments on isolated rat mast cells also indicate that ciprofloxacin at concentrations of 0.1 to 100 mg/L has histamine liberating properties.
Bronchodilatory Effects
Ciprofloxacin was tested on isolated guinea-pig trachea at concentrations of 0.0001 to 10 mg/L. It produced a dose-related small but significant relaxation of respiratory airway smooth muscle. It has, however, no effect on leukotriene D4 and histamine-induced contractions at these doses.
CNS Effects
Ciprofloxacin was administered orally to 4 groups of 1 cat each under chloralose-urethane anaesthesia at doses of 0, 10, 20 and 100 mg/kg. No effects were observed on neuromuscular transmission, flexor reflex, or blood pressure.
Gastrointestinal Effects
Ciprofloxacin was administered orally to 4 groups of 20 mice each at doses of 0, 10, 30, and 100 mg/kg, 40 minutes prior to a 15% charcoal suspension. No effect was observed in intestinal charcoal transit time. When given to 3 groups of 20 rats each at doses of 0, 30 or 100 mg/kg, no gastric lesions were observed on sacrificing the animals after 5 hours.
When given intraduodenally to 3 groups of 8 rats each at doses of 0, 10 and 100 mg/kg, no increase in basal gastric acid secretion was observed on perfusion of the stomach.
Effect on Blood Glucose and Serum Triglycerides
Four groups of six fasting rats each were given intravenous injections of 0, 3, 10, and 30 mg/kg respectively. A slight but significant increase in blood glucose concentrations 60 minutes and 240 minutes post dose was observed in the 3 and 10 mg/kg groups but not in the 30 mg/kg group in comparison to controls.
At 60 minutes post dose, the serum triglyceride concentrations were slightly but significantly reduced in all three groups. This effect was not dose-related. At 120 minutes, the concentration was slightly elevated in the 30 mg/kg group.
Human Pharmacology
Pharmacokinetics
The relative bioavailability of oral ciprofloxacin, given as a tablet, is between 70 and 80 per cent compared to an equivalent dose of IV ciprofloxacin.
Following oral administration of single doses of 250 mg, 500 mg, and 750 mg of ciprofloxacin tablets respectively to groups of 3 healthy male volunteers (age: 22.8 ± 3.5 years, weight: 68.5 ± 9.4 kg), ciprofloxacin was absorbed rapidly and extensively from the gastrointestinal tract.
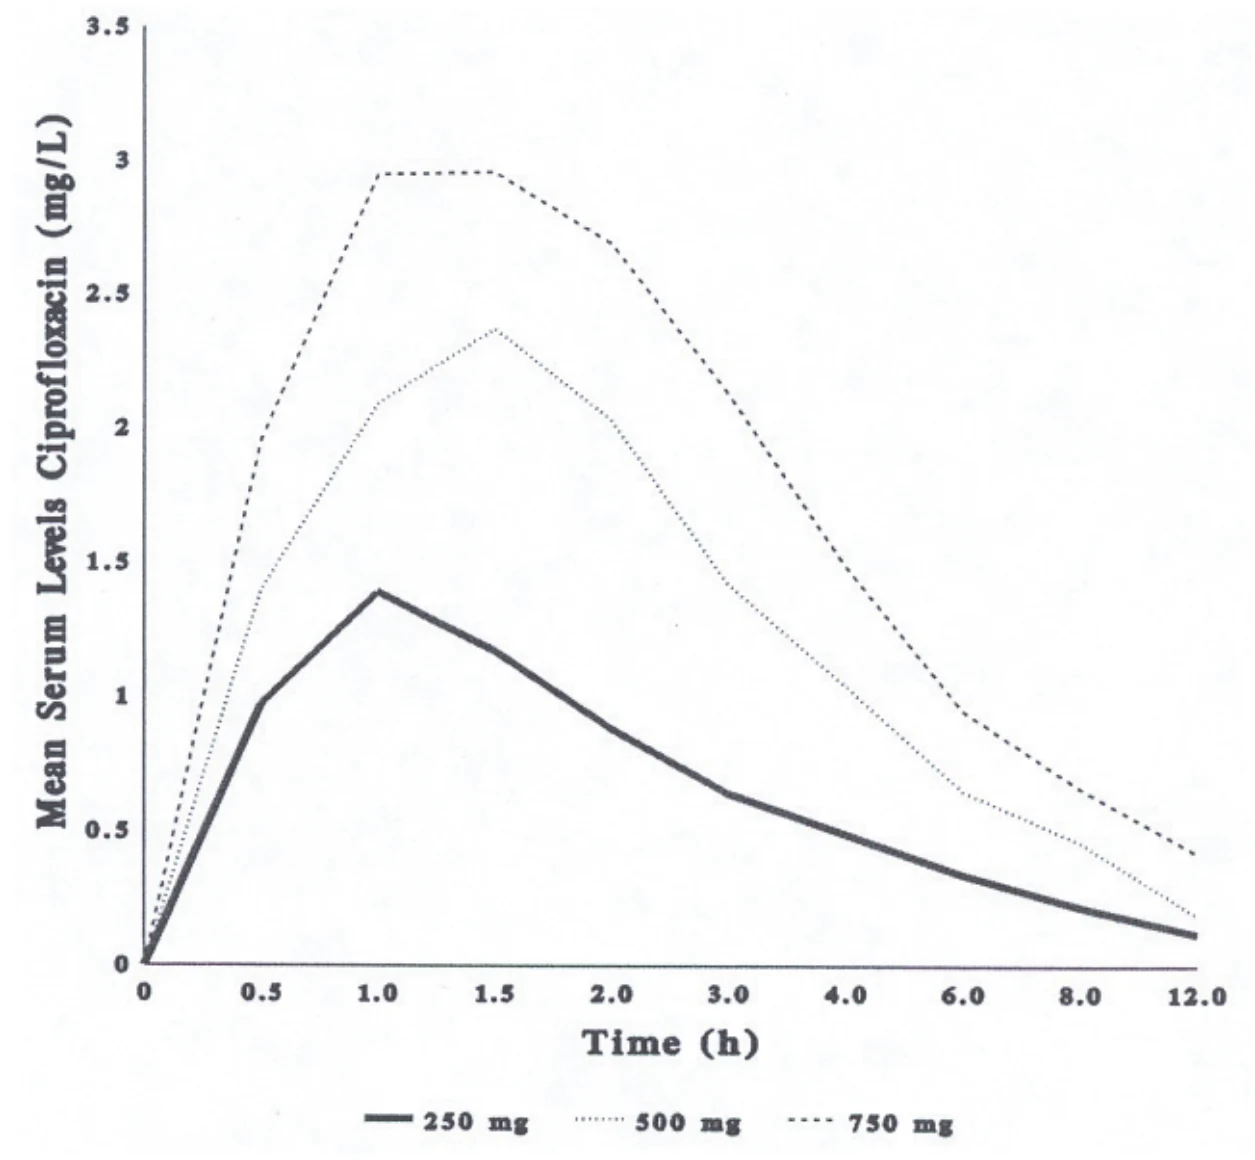
Maximum serum concentrations (Cmax) increased dose-proportionally and were attained 1 to 2 hours after oral dosing. The total areas under the serum concentration-time curves (AUC) were also increased in proportion to dose. Mean concentrations 12 hours after dosing with 250 mg, 500 mg, or 750 mg were 0.1, 0.2, and 0.4 mg/L, respectively. The serum elimination half-lives (t½) were between 4 and 6 hours. (See Table 3 and Figure 1.)
Table 3: Pharmacokinetic Parameters Following a Single Oral Dose of Ciprofloxacin Tablets in Healthy Volunteers
| Dose | 250 mg | 500 mg | 750 mg |
| Cmax (mg/L) | 1.42 | 2.60 | 3.41 |
| t½ (hr) | 4.19 | 4.87 | 5.34 |
| AUG0-∞ (mg•h/L) | 5.43 | 10.60 | 15.03 |
| tmax (hr) | 1.11 | 1.11 | 1.56 |
Similar values were obtained following the oral administration of multiple doses every 12 hours for 7 days (see Table 4).
Table 4: Mean Pharmacokinetic Parameters of Ciprofloxacin at Steady State in Healthy Volunteers
| Regimen | AUC0-12 (mg.h/L) | Cmax (mg/L) | Tmax (h) |
| Ciprofloxacin 500 mg PO q12h | 13.7 | 2.97 | 1.23 |
Figure 1: Mean Ciprofloxacin Serum Concentration After Single Oral Doses
Tablets
Metabolism and Excretion
Ciprofloxacin is largely excreted unchanged both renally and, to a small extent, extra-renally. Small concentrations of 4 metabolites have been reported: Desethyleneciprofloxacin (M1) (1.8%), sulphociprofloxacin (M2) (5.0%), oxociprofloxacin (M3) (9.6%) and formylciprofloxacin (M4) (0.1%).
Following the oral administration of a single 259 mg dose of 14C-labelled ciprofloxacin to six healthy male volunteers (age: 25.0 ± 1.46 years, weight: 70.0 ± 3.39 kg), approximately 94% of the dose was recovered in the urine and feces over five days. Most of the radioactivity was recovered in the urine (55.4%). Unchanged ciprofloxacin was the major radioactive moiety identified in both urine and feces, accounting for 45% and 25% of the dose, respectively. Total (urine and feces) excretion of all metabolites was 18.8%.
Table 5 shows urinary recovery data from another trial where healthy subjects were administered a single dose of ciprofloxacin in tablet form.
Table 5: Mean Urinary Excretion of Ciprofloxacin
| Hours After Oral Administration of a Single Tablet | ||||
| 0 – 2 | 2 – 4 | 4 – 8 | 8 – 12 | |
| Urine Concentration mg/mL (±S.D.) | ||||
| 250 mg po | 205 (±89) | 163 (±145) | 101 (±65) | 32 (±28) |
| 500 mg po | 255 (±204) | 358 (±206) | 117 (±86) | 26 (±10) |
| 750 mg po | 243 (±143) | 593 (±526) | 169 (±131) | 55 (±36) |
| Amount Excreted mg (±S.D.) | ||||
| 250 mg dose | 54.38 (±36.22) | 26.79 (±11.78) | 22.84 (±6.79) | 8.90 (±4.25) |
| 500 mg dose | 64.51 (±25.06) | 47.37 (±15.65) | 39.54 (±11.17) | 15.52 (±5.39) |
| 750 mg dose | 68.90 (±41.85) | 72.43 (±33.13) | 61.07 (±21.68) | 28.11 (±7.64) |
Factors Influencing the Pharmacokinetics
Age (Elderly)
In 4 females and 6 males, (age: 67 ± 4 years, weight: 65 ± 6 kg) with normal renal function for their age, given a single oral dose of 250 mg, maximum ciprofloxacin serum concentrations and areas under the serum concentration time curves were significantly higher than in 10 male younger volunteers (age: 24 ± 3 years, weight: 72 ± 9 kg). The time to peak serum concentrations, overall elimination half-life and urinary recovery of ciprofloxacin were similar in both age groups.
Table 6: Comparison of Pharmacokinetic Parameters between Healthy Elderly and Healthy Younger Volunteers Following Oral Administration of a Single 250 mg Tablet
| Parameter | Elderly Volunteers (mean ± S.D.) | Younger Volunteers (mean ± S.D.) |
| Cmax (mg/L) | 1.8 ± 0.5 | 1.3 ± 0.4 |
| tmax (hr) | 1.2 ± 0.3 | 1.2 ± 0.1 |
| t½ (hr) | 3.7 ± 0.9 | 3.3 ± 0.6 |
| Total AUC (mg·h/L) | 7.25 ± 2.45 | 5.29 ± 1.21 |
| % Dose Urinary Recovery after 24 hours | 43 | 43 |
Impaired Renal Function
Ciprofloxacin is eliminated primarily by renal excretion. However, the drug is also metabolized and partially cleared through the biliary system of the liver and through the intestine. This alternate pathway of drug elimination appears to compensate for the reduced renal excretion of patients with renal impairment. Nonetheless, some modification of dosage is recommended, particularly for patients with severe renal dysfunction.
The pharmacokinetics of ciprofloxacin following a single oral dose of 250 mg in 6 patients (5 male, 1 female, age: 51 ± 9 years) with normal renal function (see Group I, Table 7) were compared to 6 patients (3 male, 3 female, age: 63 ± 6 years) with renal impairment (see Group II, Table 7) and to 5 patients (2 male, 3 female, age: 63 ± 6 years) with end-stage renal failure, treated by haemodialysis (see Group III, Table 7). Patients with renal insufficiency had significantly increased AUCs, prolonged (about 2-fold) elimination half-lives, and decreased renal clearances.
Haemodialysis resulted in a minimal decrease in plasma levels. From the dialysate concentrations, it can be estimated that no more than 2% of the dose was removed by dialysis over 4 hours, which was less than the amount lost in the urine over 24 hours in patients of Group II (see Table 7).
Table 7: Mean Pharmacokinetic Parameters for Ciprofloxacin Following Oral Administration of a Single 250 mg Tablet in Healthy Volunteers and in Patients with Renal Insufficiency
| Group | Creatinine Clearance (mL/s/1.73 m2) (mL/min/1.73 m2) | Parameter | |||||
| Cmax (mg/L) | tmax (h) | Half-Life (h) | Total AUC (mg·h/mL) | Renal Clearance (mL/min) | % Dose Urinary Recovery (0-24 h) | ||
| I | >1.0 (>60) | 1.52 (±0.21) | 1.0 (±0.0) | 4.4 (±0.2) | 6.94 (±0.97) | 232.9 (±44.8) | 37.0 (±3.7) |
| II | <0.33 (<20) | 1.70 (±0.41) | 1.7 (±0.5) | 8.7 (±0.9) | 14.36 (±3.5) | 18.3 (±3.5) | 5.3 (±1.7) |
| III | End-Stage Renal Failure Treated by Hemodialysis | 2.07 (±0.23) | 1.6 (±0.2) | 5.8 (±0.9) | 15.87 (±2.0) | ||
Hepatic Impairment
In studies in patients with stable chronic cirrhosis (with mild to moderate hepatic impairment), no significant changes in ciprofloxacin pharmacokinetics have been observed. In a study of 7 cirrhotic patients and healthy volunteers given ciprofloxacin 750 mg every 12 hours for a total of nine doses followed by a 1 week washout and then a 30 minute infusion of ciprofloxacin I.V. 200 mg, there was no difference in pharmacokinetics between patients with stable chronic cirrhosis (with mild to moderate hepatic impairment) and healthy volunteers.
Food
The administration of ciprofloxacin with food delayed absorption, as shown by an increase of approximately 50% in time to peak concentrations, but did not cause other changes in the pharmacokinetics of ciprofloxacin.
Theophylline
Studies with immediate-release ciprofloxacin have shown that concomitant administration of ciprofloxacin with theophylline decreases the clearance of theophylline, resulting in elevated serum theophylline levels and increased risk of a patient developing CNS or other adverse reactions.
Caffeine and Other Xanthine Derivatives
Ciprofloxacin decreases caffeine clearance and inhibits the formation of paraxanthine after caffeine administration.
Upon concurrent administration of ciprofloxacin and pentoxifylline (oxpentifylline)-containing products, raised serum concentrations of this xanthine derivative were reported.
Class IA or III Antiarrhythmics
Precaution should be taken when using ciprofloxacin together with class IA or III antiarrhythmics as ciprofloxacin may have an additive effect on QT interval (see WARNINGS AND PRECAUTIONS).
Multivalent Cations
Absorption of ciprofloxacin is significantly reduced by concomitant administration of multivalent cation-containing products such as magnesium/aluminum antacids, lanthanum carbonate, sucralfate, Videx® (didanosine) chewable/buffered tablets or pediatric powder, mineral supplements or products containing calcium, iron, or zinc.
Probenecid
Co-administration of probenecid (1000 mg) with ciprofloxacin (500 mg) orally resulted in about 50% reduction in the ciprofloxacin renal clearance and a 50% increase in its concentration in the systemic circulation.
Clozapine
Following concomitant administration of 250 mg ciprofloxacin for 7 days, serum concentrations of clozapine and n-desmethylclozapine were increased by 29% and 31%, respectively (see WARNINGS AND PRECAUTIONS).
Lidocaine
It was demonstrated in healthy subjects that concomitant use of lidocaine with ciprofloxacin, a moderate inhibitor of CYP450 1A2 isozyme, reduces clearance of intravenous lidocaine by 22%. Ciprofloxacin may increase the systemic toxicity of lidocaine.
Ropinirole
In a clinical study it was shown that concomitant use of ropinirole with ciprofloxacin, a medium inhibitor of the CYP450 1A2 isozyme, resulted in increases in Cmax and AUC of ropinirole of 60% and 84%, respectively. Ciprofloxacin may increase the systemic toxicity of ropinirole.
Sildenafil
Cmax and AUC of sildenafil were increased approximately two-fold in healthy subjects after an oral dose of 50 mg was given concomitantly with 500 mg ciprofloxacin. Therefore, caution should be used prescribing ciprofloxacin concomitantly with sildenafil, taking into consideration the risks and the benefits.
Vitamin K Antagonists
Simultaneous administration of ciprofloxacin with a vitamin K antagonist may augment its anticoagulant effects. The risk may vary with the underlying infection, age, and general status of the patient so that the contribution of ciprofloxacin to the increase in INR (international normalized ratio) is difficult to assess. The INR should be monitored frequently during and shortly after co-administration of ciprofloxacin with a vitamin K antagonist (e.g. warfarin and acenocoumarol).
Serum Protein Binding
Serum protein binding of ciprofloxacin is between 19% to 40%, which is not likely to be high enough to cause significant protein binding interactions with other drugs.
Tissue Concentrations
In one study, the apparent volume of distribution (Vdarea) of ciprofloxacin was estimated from the kinetic data recorded after oral doses and found to be approximately 3.5 L/kg, which suggests substantial tissue penetration.
The distribution of ciprofloxacin was observed to be rapid in healthy volunteers receiving various single and multiple intravenous doses. Fitting the serum profile to a two compartment model provides a distribution phase with a half-life between 0.2 and 0.4 hours. The volume of distribution at steady state (VdSS) and Vdarea were between 1.7 and 2.7 L/kg respectively. The
volume of the central compartment was between 0.16 and 0.63 L/kg, which approximates the total volume of extracellular water.
Single intravenous doses of 100, 150, and 200 mg ciprofloxacin were administered to nine healthy volunteers to determine the excretion and distribution of ciprofloxacin following intravenous administration and to assess the effect of dose size on pharmacokinetic parameters.
Analysis with a three-compartmental pharmacokinetic model quantified approximate sizes and kinetics of distribution into two peripheral compartments: a rapidly equilibrating compartment (V2) with a high intercompartmental clearance rate, accounting for the rapid decline in ciprofloxacin concentrations in serum immediately following drug infusion; and a second, slowly equilibrating tissue compartment with relatively slow intercompartmental clearance. This would contribute to the prolonged terminal half-life (4 to 5 h) of ciprofloxacin I.V.
The results of this study were as follows: volume of distribution at steady state (Vss) was determined to be between 2.0 and 2.9 L/kg. Volumes in each compartment were determined to be: central compartment 0.2 - 0.4, peripheral V2 0.6 - 0.8 and peripheral V3 1.2 - 1.6 L/kg. Table 8 summarizes the results of tissue and fluid penetration of ciprofloxacin in man.
Table 8: Distribution of Ciprofloxacin in Human Tissue/Fluid
| Tissue/Fluid | No. of Patients | Single Dose of Ciprofloxacin | Peak Concentration (mg/kg or mg/L) | Mean Serum Concentration (mg/L) | Time After Dose (hr) |
| Skin Blister Fluid | 6 | 500 mg po | 1.4 ± 0.36 | 2.3 ± 0.7 | 1 – 6 |
| Bone | 4 | 750 mg po | 1.4 ± 1.0 | 2.9 ± 2.2 | 2 – 4 |
| Gynecological Tissue | 18 | 500 mg po | 1.3 ± 0.66 to 1.6 ± 0.97 | 1.4 ± 0.87 | 2 – 4 |
| Prostatic Tissue | 1 | 500 mg po | 3.76 | 1.84 | 2.5 |
| Muscle | 4 | 250 mg po | 2.4 ± 1.0 | 2.9 ± 2.2 | 2 – 4 |
| Nasal Secretions | 20 | 500 mg po | 1.4 ± 0.81 | 1.8 ± 0.48 | 1 – 3 |
MICROBIOLOGY
Mechanism of Action
The bactericidal action of ciprofloxacin results from inhibition of enzymes topoisomerase II (DNA gyrase) and topoisomerase IV, which are required for bacterial DNA replication, transcription, repair, and recombination.
Drug Resistance
The mechanism of action of fluoroquinolones, including ciprofloxacin, is different from that of penicillins, cephalosporins, aminoglycosides, macrolides, and tetracyclines; therefore, microorganisms resistant to these classes of drugs may be susceptible to ciprofloxacin and other fluoroquinolones. There is no known cross-resistance between ciprofloxacin and other classes
of antimicrobials. In vitro resistance to ciprofloxacin develops slowly by multiple step mutations. Resistance to ciprofloxacin due to spontaneous mutations occurs at a general frequency of between < 10-9 to 1 x 10⁻⁶.
Activity in vitro and in vivo
Ciprofloxacin has in vitro activity against a wide range of gram-positive and gram-negative microorganisms. Ciprofloxacin is slightly less active when tested at acidic pH. The inoculums size has little effect when tested in vitro. The minimal bactericidal concentration (MBC) generally does not exceed the minimal inhibitory concentration (MIC) by more than a factor of 2. Ciprofloxacin has been shown to be active against most strains of the following microorganisms, both in vitro and in clinical infections:
Aerobic gram-positive microorganisms
Enterococcus faecalis (many strains are only moderately susceptible.) Staphylococcus aureus (methicillin-susceptible strains only)
Staphylococcus epidermidis (methicillin-susceptible strains only)
Staphylococcus saprophyticus
Streptococcus pyogenes
Aerobic gram-negative microorganisms
Campylobacter jejuni Proteus mirabilis
Citrobacter diversus Proteus vulgaris
Citrobacter freundii Providencia rettgeri
Enterobacter cloacae Providencia stuartii
Escherichia coli Pseudomonas aeruginosa Haemophilus influenzae Salmonella typhi
Haemophilus parainfluenzae Serratia marcescens Klebsiella pneumoniae Shigella boydii
Moraxella catarrhalis Shigella dysenteriae
Morganella morganii Shigella flexneri
Neisseria gonorrhoeae Shigella sonnei
The following in vitro data are available, but their clinical significance is unknown. Ciprofloxacin exhibits in vitro minimum inhibitory concentrations (MICs) of 1 μg/mL or less against most ( ≥ 90%) strains of the following microorganisms; however, the safety and effectiveness of ciprofloxacin in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trails.
Aerobic gram-positive microorganisms
Staphylococcuc haemolyticus
Staphylococcus hominis
Aerobic gram-negative microorganisms
Acetinobacter iwoffii Salmonella enteritidis
Aeromonas hydrophila Vibrio cholerae
Edwardsiella tarda Vibrio parahaemolyticus Enterobacter aerogenes Vibrio vulnificus
Legionella pneumophila Yersinia enterocolitica Pasteurella multocida
Most strains of Burkholderia cepacia, and some strains of Stenotrophomonas maltophilia are resistant to ciprofloxacin as are most anaerobic bacteria, including Bacteroides fragilis and Clostridium difficile.
Susceptibility Testing
Dilution Techniques: Quantitative methods are used to determine antimicrobial minimal inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a dilution method (1) (broth or agar) or equivalent with standardized inoculum concentrations and standardized concentrations of ciprofloxacin powder. The MIC values should be interpreted according to the criteria outlined in Table 9:
Diffusion Techniques: Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure (2) requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 5 µg ciprofloxacin to test the susceptibility of microorganisms to ciprofloxacin.
Reports from the laboratory providing results of the standard single-disk susceptibility test with a 5 µg ciprofloxacin disk should be interpreted according to the criteria outlined in Table 9.
Interpretation involves correlation of the diameter obtained in the disk test with the MIC for ciprofloxacin.
Table 9: Susceptibility Interpretative Criteria for Ciprofloxacin
| MIC (μg/mL) | Zone Diameter (mm) | |||||
| Species | S | I | R | S | I | R |
| Enterobacteriacae | ≤ 1 | 2 | ≥ 4 | ≥ 21 | 16-20 | ≤ 15 |
| Enterococcus faecalis | ≤ 1 | 2 | ≥ 4 | ≥ 21 | 16-20 | ≤ 15 |
| Methicillin susceptible Staphylococcus species | ≤ 1 | 2 | ≥ 4 | ≥ 21 | 16-20 | ≤ 15 |
| Pseudomonas aeruginosa | ≤ 1 | 2 | ≥ 4 | ≥ 21 | 16-20 | ≤ 15 |
| Haemophilus influenzae | ≤ 1a | g | g | ≥ 21b | g | g |
| Haemophilus parainfluenzae | ≤ 1a | g | g | ≥ 21b | g | g |
| Streptococcus pyogenes | ≤ 1c | 2c | ≥ 4c | ≥ 21d | 16 – 20d | ≤ 15d |
| Neisseria gonorrhoeae | ≤ 0.06e | 0.12 – 0.15e | ≤ 1e | ≥ 41f | 28 – 40f | ≤ 27f |
Abbreviations: I = Intermediate; MIC = minimum inhibitory concentration; μg = microgram; mL = milliliter; mm = millimiter; R = Resistant; S = Susceptible
a This interpretive standard is applicable only to broth microdilution susceptibility tests with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium (HTM). (1) b This zone diameter standard is applicable only to tests with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium (HTM). (2)
c These interpretive standards are applicable only to broth microdilution susceptibility tests with streptococci using cation-adjusted Mueller-Hinton broth with 2-5% lysed horse blood.
d These zone diameter standards are applicable only to tests performed for streptococci using Mueller-Hinton agar supplemented with 5% sheep blood incubated in 5% CO2.
e This interpretive standard is applicable only to agar dilution test with GC agar base and 1% defined growth supplement.
f This zone diameter standard is applicable only to disk diffusion tests with GC agar base and 1% defined growth supplement.
g The current absence of data on resistant strains precludes defining any results other than “Susceptible”. Strains yielding MIC results suggestive of a “nonsusceptible” category should be submitted to a reference laboratory for further testing.
A report of “Susceptible” indicates that the pathogen is likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable. A report of “Intermediate” indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high dosage of drug can be used. This category also provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of “Resistant” indicates that the pathogen is not likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable; other therapy should be selected.
Quality Control: Standardized susceptibility test procedures require the use of laboratory control microorganisms to control the technical aspects of the laboratory procedures. For dilution technique, standard ciprofloxacin powder should provide the MIC values according to criteria outlined in Table 10. For diffusion technique, the 5 μg ciprofloxacin disk should provide the zone diameters outlined in Table 10.
Table 10: Quality Control for Susceptibility Testing
| Strains | MIC Range (μg/mL) | Zone Diameter (mm) |
| Enterococcus faecalis ATCC 29212 | 0.25 – 2 | - |
| Escherichia coli ATCC 25922 | 0.004 - 0.015 | 30 – 40 |
| Haemophilus influenzae ATCC 49247 | 0.004 - 0.03a | 34 – 42d |
| Pseudomonas aeruginosa ATCC 27853 | 0.25 – 1 | 25 – 33 |
| Staphylococcus aureus ATCC 29213 | 0.12 – 0.5 | - |
| Staphylococcus aureus ATCC 25923 | - | 22 – 30 |
| Neisseria gonorrhoeae ATCC 49226 | 0.001 – 0.008b | 48 – 58e |
| C. jejuni ATCC 33560 | 0.06 – 0.25 and 0.03 – 0.12c | - |
Abbreviations: ATCC = American Type Culture Collection; MIC = minimum inhibitory concentration; μg = microgram; mL = milliliter; mm = millimiter
a This quality control range is applicable to only H. influenzae ATCC 49247 tested by a broth microdilution procedure using Haemophilus Test Medium (HTM). (1)
b N. gonorrhoeae ATCC 49226 tested by agar dilution procedure using GC agar and 1% defined growth supplement in a 5% CO2 environment at 35-37°C for 20-24 hours.(2)
c C. jejuni ATCC 33560 tested by broth microdilution procedure using cation adjusted Mueller Hinton broth with
2.5-5% lysed horse blood in a microaerophilic environment at 36-37°C for 48 hours and for 42°C at 24 hours, respectively.
d These quality control limits are applicable to only H. influenzae ATCC 49247 testing using Haemophilus Test
Medium (HTM). (2)
e These quality control limits are applicable only to tests conducted with N. gonorrhoeae ATCC 49226 performed by disk diffusion using GC agar base and 1% defined growth supplement.
TOXICOLOGY
Acute Toxicity
Species Mode of Administration LD50 (mg/kg)
Mouse p.o. approx. 5000 Rat p.o. approx. 5000 Rabbit p.o. approx. 2500 Mouse i.v. approx. 290 Rat i.v. approx. 145 Rabbit i.v. approx. 125 Dog i.v. approx. 250
Chronic Toxicity
Subacute Tolerability Studies over 4 Weeks
Oral administration: Doses up to and including 100 mg/kg were tolerated without damage by rats. Pseudoallergic reactions due to histamine release were observed in dogs.
Parenteral administration: In the highest-dose group in each case (rats 80 mg/kg and monkeys 30 mg/kg), crystals containing ciprofloxacin were found in the urine sediment. There were also changes in individual renal tubules, with typical foreign-body reactions dues to crystal-like precipitates. These changes are considered secondary inflammatory foreign-body reactions due to the precipitation of a crystalline complex in the distal renal tubule system.
Subchronic Tolerability Studies over 3 Months
Oral administration: All doses up to and including 500 mg/kg were tolerated without damage by rats. In monkeys, crystalluria and changes in the renal tubules were observed in the highest-dose group (135 mg/kg).
Parenteral administration: Although the changes in the renal tubules observed in rats were in some cases very slight, they were present in every dose group. In monkeys they were found only in the highest-dose group (18 mg/kg) and were associated with slightly reduced erythrocyte counts and hemoglobin values.
Chronic Tolerability Studies over 6 Months
Oral administration: Doses up to and including 500 mg/kg and 30 mg/kg were tolerated without damage by rats and monkeys, respectively. Changes in the distal renal tubules were again observed in some monkeys in the highest-dose group (90 mg/kg).
Parenteral administration: In monkeys slightly elevated urea and creatinine concentrations and changes in the distal renal tubules were recorded in the highest-dose group (20 mg/kg).
Carcinogenicity
In carcinogenicity studies in mice (21 months) and rats (24 months) with doses up to approximately 1000 mg/kg bw/day in mice and 125 mg/kg bw/day in rats (increased to 250 mg/kg bw/day after 22 weeks), there was no evidence of a carcinogenic potential at any dose level.
Reproduction Toxicology
Fertility studies in rats: Fertility, the intrauterine and postnatal development of the young, and the fertility of F1 generation were not affected by ciprofloxacin.
Embryotoxicity studies: These yielded no evidence of any embryotoxic or teratogenic action of ciprofloxacin.
Perinatal and postnatal development in rats: No effects on the perinatal or postnatal development of the animals were detected. At the end of the rearing period histological investigations did not bring to light any sign of articular damage in the young.
Mutagenicity
Eight in vitro mutagenicity tests have been conducted with ciprofloxacin. Test results are listed below:
Salmonella: Microsome Test (Negative)
E. coli: DNA Repair Assay (Negative)
Mouse Lymphoma Cell Forward Mutation Assay (Positive)
Chinese Hamster V79 Cell HGPRT Test (Negative)
Syrian Hamster Embryo Cell Transformation Assay (Negative)
Saccharomyces cerevisiae: Point Mutation Assay (Negative)
Mitotic Crossover and Gene Conversion Assay (Negative)
Rat Hepatocyte Primary Culture DNA Repair Assay (LIDS) (Positive)
Two of the eight tests were positive, but results of the following four in vivo test systems gave negative results:
Rat Hepatocyte DNA Repair Assay
Micronucleus Test (Mice)
Dominant Lethal Test (Mice)
Chinese Hamster Bone Marrow
Special Tolerability Studies
It is known from comparative studies in animals, both with the older gyrase inhibitors and the more recent ones, that this substance class produces a characteristic damage pattern. Kidney damage, cartilage damage in weight-bearing joints of immature animals, and eye damage may be encountered.
Renal Tolerabilitv: The crystallization observed in the animal studies occurred preferentially under pH conditions that do not apply in man.
Compared to rapid infusion, a slow infusion of ciprofloxacin reduces the danger of crystal precipitation.
The precipitation of crystals in renal tubules does not immediately and automatically lead to kidney damage. In the animal studies, damage occured only after high doses, with
correspondingly high levels of crystalluria. For example, although they always caused crystalluria, even high doses were tolerated over 6 months without damage and without foreign-body reactions occurring in individual distal renal tubules.
Damage to the kidneys without the presence of crystalluria has not been observed. The renal damage observed in animal studies must not, therefore, be regarded as a primary toxic action of ciprofloxacin on the kidney tissue, but as typical secondary inflammatory foreign-body reactions due to the precipitation of a crystalline complex of ciprofloxacin, magnesium, and protein.
Articular tolerabilitv studies: As it is also known for other gyrase inhibitors, ciprofloxacin causes damage to the large, weight-bearing joints in immature animals.
The extent of the cartilage damage varies according to age, species, and dose; the damage can be reduced by taking the weight off the joints. Studies with mature animals (rat, dog) revealed no evidence of cartilage lesions.
Retina tolerability studies: Ciprofloxacin binds to the melanin containing structures including the retina. Potential effects of ciprofloxacin on the retina were assessed in various pigmented animal species. Ciprofloxacin treatment had no effect on the morphological structures of the retina and on electroretinographic findings.
REFERENCES
- 1.
CLSI (Clinical and Laboratory Standards Institute). Methods for Dilution
Antimicrobial Susceptibility Tests for Bacteria That Grow Aerobically; Approved Standard. CLSI Document M7-A8, Vol. 29, No. 2. Eighth Edition ed. CLSI, Wayne, PA2009.
- 2.
CLSI (Clinical and Laboratory Standards Institute). Performance Standards for
Antimicrobial Disk Susceptibility Tests; Approved Standard. CLSI Document M2-A10 Vol. 29, No.1. Tenth Edition ed. CLSI, Wayne, PA2009.
- 3. Aigner KR, Dalhoff A. Penetration activities of ciprofloxacin into muscle, skin and fat following oral administration. J Antimicrob Chemother 1986;18:644-645.
- 4.
Aldridge KE, Schiro DD, Tsai L, Janney A, Sanders CV, Marier RL. Ciprofloxacin
(BAY o 9867) and in vitro comparison with other broad spectrum antibiotics. Curr Ther Res 1985;37(4):754-762.
- 5.
Auckenthaler R, Michea-Hamzehpour M, Pechere JC. In-vitro activity of newer quinolones against aerobic bacteria. J Antimicrob Chemother 1986;17(Suppl.B):29-
39.
- 6.
Barry AL, Fass RJ, Anhalt JP, Neu HC, Thornsberry C, Tilton RC, Painter BG,
Washinton JA. Ciprofloxacin disk susceptibility tests: interpretive zone size standards for 5 µg disks. J Clin Microbiol 1985;21(6):880-883.
- 7. Bauernfeind A, Petermuller C. In vitro activity of ciprofloxacin, norfloxacin and nalidixic acid. Eur J Clin Microbiol 1983;2(2):111-115.
- 8. Bayer A, Gajewska A, Stephens M, Marshal-Stark J, Pathy J. Pharmacokinetics of ciprofloxacin in the elderly, Respiration 1987;51:292-295.
- 9. Beermann D, Scholl H, Wingender W, Forster D, Beubler E. Metabolism of ciprofloxacin in man. In Neu HC & Weuta H (Eds) 1st International Ciprofloxacin Workshop, Leverkusen 1985, pp. 141-146, Excerpta Medica, Amsterdam, 1986.
- 10.
CLSI (Clinical and Laboratory Standards Institute). Methods for Antimicrobial
Dilution and Disk Susceptibility Testing of Infrequently Isolated or Fastidious Bacteria; Approved Standard. Document M45-A2, Second Edition ed. CLSI, Wayne, PA2010.
- 11.
Crump B, Wise R, Dent J. Pharmacokinetics and tissue penetration of ciprofloxacin.
Antimicrob Agents Chemother 1983;24(5):784-786.
- 12.
Fass RJ. Treatment of skin and soft tissue infections with oral ciprofloxacin. J
Antimicrob Chemother 1986; 18 (Suppl.D):153-157.
- 13. Fass RJ. Efficacy and safety of oral ciprofloxacin for treatment of serious urinary tract infections Antimicrob Agents Chemother 1987;31:148-150.
- 14. Fass RJ. Efficacy and safety of oral ciprofloxacin in the treatment of serious respiratory infections. Am J Med 1987;82 (Suppl 4A):202-207.
- 15. Fong IG, Ledbetter WH, Van en broucke C, Simbul M, Rahm V. Ciprofloxacin concentrations in bone and muscle after oral dosing. Antimicrob Agents Chemother 1986;29:405-408.
- 16. Gasser TC, Ebert SC, Graversen PHm, Madsen PO. Ciprofloxacin pharmacokinetics with normal and impaired renal function. Antimicrob Agents and Chemother 1987;31:709-712.
- 17. Giamarellou H, Galanakis N, Dendrinos C, Stefanou J, Daphnis E. Evaluation of ciprofloxacin in the treatment of Pseudomonas aeruginosa infections. Eur J Clinical Microbiol 1986;5:232-235.
- 18. Gonzalez MA, Moranchel AH, Duran S, Pichardo A, Magana JL. Multiple dose ciprofloxacin dose ranging and kinetics. Clin Pharmacol Ther 1985;37:633-637.
- 19. Greenberg RNM, Kennedy DJ, Reilly PM, Luppen KL, Weinandt WJ. Treatment of bone, joint and soft tissue infections with oral ciprofloxacin. Antimicrob Agents Chemother 1987;31:151-155.
- 20. Greenberg RNM, Tice AD, Marsh PK, Craven PC, Reilly PM. Randomized trial of ciprofloxacin compared with other antimicrobial therapy in the treatment of osteomyelitis. Am J Med 1987;82 (Suppl.4A):266-269.
- 21. Honeybourne D, Andrews JM, Ashby JP, Lodwick R, Wise R. Evaluation of the penetration of ciprofloxacin and amoxicillin into the bronchial mucosa. Thorax. 1988 Sep;43(9):715-9.
- 22.
Honeybourne D, Wise R, Andrews JM. Ciprofloxacin penetration into lungs. Lancet
1987;2031:1040.
- 23.
LeBel M, Bergeron MG, Vallee F, Fiset C, Chasse G. Pharmacokinetics &
Pharmacodynamics of ciprofloxacin in cystic fibrosis patients. Antimicrob Agents Chemother 1986;30:260-266.
- 24. Ledergerber B, Bettex JD, Joos B, Flepp M, Luethy R. Effect of standard breakfast on drug absorption and multiple-dose pharmacokinetics of ciprofloxacin. Antimicrob Agents Chemother 1985;27(3):350-352.
- 25.
Licitra CM, Brooks RG, Siegler BE. Clinical Efficacy and levels of ciprofloxacin in
Tissue in patients with soft tissue infection. Antimicrob Agents Chemother 1987;31:805-807.
- 26. Ramirez-Ronda CH, Saavedra S, Rivera-Vazques CR. Comparative, double-blind study of oral ciprofloxacin and intravenous cefotaxime in skin and skin structure infections. Am J Med 1987;82 (Suppl. 4A):220-223.
- 27. Raoof S, Wollschager C, Khan FA. Ciprofloxacin increases serum levels of theophylline. Am J Med 1987;84 (Suppl. 4A):115-118.
- 28. Ratcliffe NT, Smith JT. Effects of magnesium on the activity of 4-quinolone antibacterial agents. J Pharm Pharmacol 1983; 35(Suppl):61P.
- 29.
Schacht P, Arcieri G, Branolte J, Bruck H, Chysky V. Worldwide Clinical Data on
Efficacy and Safety of Ciprofloxacin. Infection, 1988;(Suppl.1), 16:29-43.
- 30.
Schluter G. Toxicology of ciprofloxacin. In Neu HC, Weuta H (Eds) 1st International
Ciprofloxacin Workshop, Leverkusen 1985, pp. 291-296, Excerpta Medica, Amsterdam, 1986.
- 31.
Smith JT. The mode of action of 4-quinolones and possible mechanisms of resistance.
J Antimicrob Chemother 1986;18(Supp. D.):21-29.
- 32.
Wolfson JS, Hooper DC, The fluoroquinolones: Stuctures, Mechanisms of Action and
Resistance, and Spectra of Activities in Vitro. Antimicrob Agents Chemother 1985;28(4):581-586.
- 33.
Zeiler H-J. Evaluation of the In Vitro Bactericidal Action of Ciprofloxacin on Cells of
Escherichia Coli in the Logarithmic and Stationary Phases of Growth. Antimicrob Agents Chemother 1985;28(4):524-527.
- 34.
Product Monograph for CIPRO®, and CIPRO® ORAL SUSPENSION (Bayer Inc.,
Canada), Control No.150473, Date of Revision January 23, 2012.