


Product Monograph - Elocom
Recent Major Label Changes
| None at time of most recent authorization |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................. 2
Table of Contents .................................................................................................................. 2
Part 1: Healthcare Professional Information........................................................................... 4
- 1.
Indications ................................................................................................................. 4
1.1. Pediatrics ...................................................................................................................... 4
1.2. Geriatrics ....................................................................................................................... 4
- 2. Contraindications ....................................................................................................... 4
- 4.
Dosage and Administration ........................................................................................ 4
4.1. Dosing Considerations .................................................................................................. 4
4.2. Recommended Dose and Dosage Adjustment ............................................................. 5
4.4. Administration .............................................................................................................. 5
4.5. Missed Dose .................................................................................................................. 5
- 5. Overdosage ................................................................................................................ 5
- 6. Dosage Forms, Strengths, Composition, and Packaging ............................................... 6
- 7.
Warnings and Precautions .......................................................................................... 6
7.1. Special Populations ....................................................................................................... 8
7.1.1. Pregnancy ............................................................................................................ 8
7.1.2. Breastfeeding ...................................................................................................... 9
7.1.3. Pediatrics ............................................................................................................. 9
7.1.4. Geriatrics ............................................................................................................. 9
- 8.
Adverse Reactions ...................................................................................................... 9
8.1. Adverse Reaction Overview .......................................................................................... 9
8.2. Clinical Trial Adverse Reactions .................................................................................. 10
8.3. Less Common Clinical Trial Adverse Reactions .......................................................... 10
- 9.
Drug Interactions ..................................................................................................... 11
9.3. Drug-Behavioural Interactions ................................................................................... 11
9.4. Drug-Drug Interactions ............................................................................................... 11
9.5. Drug-Food Interactions ............................................................................................... 11
9.6. Drug-Herb Interactions ............................................................................................... 11
9.7. Drug-Laboratory Test Interactions ............................................................................. 11
- 10.
Clinical Pharmacology .............................................................................................. 11
10.1. Mechanism of Action ........................................................................................ 11
10.2. Pharmacodynamics ........................................................................................... 12
10.3. Pharmacokinetics .............................................................................................. 12
- 11. Storage, Stability and Disposal .................................................................................. 13
- 12. Special Handling Instructions .................................................................................... 13
Part 2: Scientific Information ............................................................................................... 14
- 13. Pharmaceutical Information ............................................................................................. 14
- 14.
Clinical Trials ..................................................................................................................... 14
14.1. Clinical Trials by Indication ............................................................................... 16
- 16. Non-Clinical Toxicology ..................................................................................................... 21
Patient Medication Information .......................................................................................... 23
Part 1: Healthcare Professional Information
1. Indications
ELOCOM® (mometasone furoate) Cream, Ointment and Lotion 0.1%:
- are indicated for the relief of the inflammatory and pruritic manifestations of corticosteroid-responsive dermatoses such as psoriasis and atopic dermatitis. The lotion formulation may be applied to scalp lesions.
- can be used for a maximum of 3 weeks duration on the body and of 5 days duration on the face, scalp, axillae and scrotum.
1.1. Pediatrics
Pediatrics (<18 years of age): Safety and efficacy of ELOCOM have not been established in pediatric patients (see 7. Warnings and Precautions, 7.1. Special Populations, 7.1.3. Pediatrics).
1.2. Geriatrics
Geriatrics (≥ 65 years of age): No overall differences in safety and effectiveness were observed between subjects greater than 65 years of age and younger subjects receiving ELOCOM Cream or Ointment. Clinical trials of ELOCOM Lotion did not include sufficient numbers of subjects aged 65 years and older to determine whether they respond differently from younger subjects. Geriatric patients may be more susceptible to the potential effects of systemic absorption. Decreased hepatic or renal function in the elderly may delay elimination (see 7. Warnings and Precautions, 7.1. Special Populations, 7.1.4. Geriatrics).
2. Contraindications
ELOCOM Cream, Ointment and Lotion 0.1% are contraindicated:
- In patients who are sensitive to mometasone furoate, to other corticosteroids or to any component of these preparations. For a complete listing, see the Dosage Forms, Composition, and Packaging section of the product monograph.
- In patients with viral (e.g. herpes or varicella) lesions of the skin, bacterial or fungal skin infections, parasitic infections, skin manifestations relating to tuberculosis or syphilis, eruptions following vaccinations, acne vulgaris, rosacea, pruritus without inflammation.
- For use in the eyes.
- For use with occlusive dressings
4. Dosage and Administration
4.1. Dosing Considerations
Patients/caregivers should be instructed to use ELOCOM for the minimum amount of time necessary to achieve the desired results because of the potential for corticosteroids to supress the hypothalamic-pituitary-adrenal (HPA) axis and cause skin atrophy (See 7. Warnings and Precautions).
ELOCOM is for topical use only and not for use on mucous membranes.
Use in pediatric patients is not recommended. Pediatric patients may be more susceptible to local and systemic toxicity from equivalent doses because of their larger skin surface to body weight ratios.
Geriatric patients may be more susceptible to the potential effects of systemic absorption. Decreased hepatic or renal function in the elderly may delay elimination.
4.2. Recommended Dose and Dosage Adjustment
ELOCOM Cream/Ointment: Apply a thin film to the affected skin areas once daily.
ELOCOM Lotion: Apply a few drops of the lotion to the affected skin areas including scalp sites once daily; massage gently and thoroughly until medication disappears.
ELOCOM Cream, Ointment or Lotion, 0.1% should be used on the face, axillae or scrotum for a maximum of 5 days. ELOCOM Lotion, 0.1% should be used on the scalp for a maximum of 5 days.
ELOCOM Cream, Ointment or Lotion, 0.1% should be used on the body for a maximum of 3 weeks. If no improvement is seen within 2 weeks, reassessment of diagnosis and treatment may be necessary.
Therapy should be discontinued when control is achieved. Continue an emollient as maintenance therapy.
Geriatrics (≥ 65 years of age): ELOCOM should be used with caution due to increased risk of renal or hepatic impairment in this population. The minimum quantity should be used for the shortest duration to achieve the desired clinical benefit (see 7. Warnings and Precautions, 7.1. Special Populations, 7.1.4. Geriatrics).
Patients with renal/hepatic impairment: The minimum quantity should be used for the shortest duration to achieve the desired clinical benefit (see 7. Warnings and Precautions, Renal).
4.4. Administration
Do not use occlusive dressings.
ELOCOM should not be applied to mucous membranes.
4.5. Missed Dose
Any missed dose should be applied as soon as possible after the missed dose is remembered. If this is close to the scheduled application time or the next dose, the subject should wait and apply the next scheduled dose. The usual schedule should be resumed thereafter.
5. Overdosage
Topically applied corticosteroids can be absorbed in sufficient amounts to produce systemic effects. Excessive prolonged use or misuses may suppress hypothalamic-pituitary-adrenal (HPA) axis function, resulting in secondary adrenal insufficiency. If symptoms of HPA axis suppression occur, ELOCOM should be gradually discontinued by reducing the frequency of application or by substituting a less potent corticosteroid, as clinically indicated. If toxic effects occur, ELOCOM should be discontinued and symptomatic therapy administered (see 7. Warnings and Precautions).
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, Composition
Description
Each gram of ELOCOM Cream 0.1% contains 1 mg mometasone furoate. ELOCOM Cream 0.1% is supplied in 15 g and 50 g tubes, boxes of one.
Each gram of ELOCOM Ointment 0.1% contains 1 mg mometasone furoate. ELOCOM Ointment 0.1% is supplied in 50 g tubes, boxes of one.
Each gram of ELOCOM Lotion 0.1% contains 1 mg mometasone furoate. ELOCOM Lotion 0.1% is supplied in 100 mL plastic bottles.
7. Warnings and Precautions
General
Patients should be advised to inform subsequent physicians of the prior use of corticosteroids.
ELOCOM should not be used under occlusion, due to increased risk of systemic exposure and infection. When used under occlusive dressing, which is contraindicated, over extensive areas or on the face, scalp, axillae or scrotum, sufficient absorption may occur to result in adrenal suppression and other systemic effects (see 7. Warnings and Precautions, Endocrine and Metabolism, Immune and Ophthalmologic).
Carcinogenesis and Genotoxicity
In genetic toxicity studies, mometasone furoate was not mutagenic in bacteria (Ames test) or mammalian (mouse lymphoma) cells and was not clastogenic in the mouse micronucleus test.
Cardiovascular
Suitable precautions should be taken when using topical corticosteroids in patients with stasis dermatitis and other skin diseases with impaired circulation.
Use of corticosteroids around chronic leg ulcers may be associated with a higher occurrence of local
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Topical | Cream / 0.1% w/w mometasone furoate | aluminum starch octenylsuccinate, hexylene glycol, hydrogenated soybean lecithin, phosphoric acid, purified water, titanium dioxide, white soft paraffin and white wax. |
| Topical | Ointment / 0.1% w/w mometasone furoate | hexylene glycol, phosphoric acid, propylene glycol monostearate, purified water, white soft paraffin and white wax. |
| Topical | Lotion / 0.1% w/w mometasone furoate | hydroxypropylcellulose, isopropyl alcohol, phosphoric acid, propylene glycol, purified water and sodium phosphate monobasic. |
hypersensitivity reactions and an increased risk of local infection.
Endocrine and Metabolism
Manifestations of hypercortisolism (Cushing’s syndrome) and reversible hypothalamic-pituitary-adrenal (HPA) axis suppression, leading to glucocorticosteroid insufficiency, can occur in some individuals as a result of increased systemic absorption of topical corticosteroids. Hyperglycemia and glucosuria may occur in some patients due to systemic absorption of topical corticosteroids (see 8. Adverse Reactions).
Conditions which augment systemic absorption include the formulation and potency of the topical corticosteroid, the application of topical corticosteroids over large body surface areas, application to intertriginous areas (such as the axillae), frequency of application, prolonged use or the addition of occlusive dressings. Other risk factors for increased systemic effects include increasing hydration of the stratum corneum, use on thin skin areas (such as the face), use on broken skin or conditions where the skin barrier may be impaired.
If patients must be treated over large body surface areas, they should be evaluated periodically for evidence of HPA axis suppression (see 7. Warnings and Precautions, Monitoring and Laboratory Tests). If HPA axis suppression or Cushing’s syndrome is observed, an attempt should be made to withdraw the drug by reducing the frequency of the application. Abrupt withdrawal of treatment may result in glucocorticosteroid insufficiency (see 8. Adverse Reactions).
Recovery of HPA axis function is generally prompt upon discontinuation of topical corticosteroids. Infrequently, signs and symptoms of glucocorticosteroid insufficiency may occur requiring supplemental systemic corticosteroids. For information on systemic corticosteroid supplementation, see prescribing information for those products.
Pediatric patients may absorb larger amounts of topical corticosteroids and thus be more susceptible to systemic toxicity from equivalent doses because of their larger skin surface to body mass ratios as compared with adults (see 7. Warnings and Precautions, 7.1. Special Populations, 7.1.3. Pediatrics).
Immune
Topical corticosteroids may increase the risk of infections including aggravation of cutaneous infection, masked infection and secondary infections. In particular, bacterial infection is encouraged by warm, moist conditions within skin-fold areas or caused by occlusive dressings. If concomitant skin infections develop, ELOCOM should be discontinued and antimicrobial therapy administered.
Monitoring and Laboratory Tests
The cosyntropin (ACTH1-24) stimulation test may be helpful in evaluating patients for HPA axis suppression.
Ophthalmologic
Topical corticosteroids should be used with caution on lesions close to the eye because systemic absorption may cause increased intraocular pressure, glaucoma or cataracts.
Visual disturbance may be reported with systemic and topical (including, intranasal, inhaled and intraocular) corticosteroid use. If a patient presents with symptoms such as blurred vision or other visual disturbances, the patient should be considered for referral to an ophthalmologist for evaluation of possible causes of visual disturbances; this may include cataract, glaucoma or rare diseases such as central serous chorioretinopathy (CSCR) which have been reported after use of systemic and topical corticosteroids.
Renal
Safety of ELOCOM has not been established in patients with renal or hepatic impairment. In case of systemic absorption, metabolism and elimination may be delayed leading to increased risk of systemic toxicity; therefore, minimum quantity should be used for the minimum duration.
Reproductive Health
Fertility
There are no data in humans to evaluate the effect of topical corticosteroids on fertility.
Sensitivity/Resistance
Local hypersensitivity reactions (see 8. Adverse Reactions) may resemble symptoms of the condition under treatment. If hypersensitivity reactions occur, the drug should be discontinued and appropriate therapy initiated.
Allergic contact dermatitis with corticosteroids is usually diagnosed by observing a failure to heal rather than noticing a clinical exacerbation. Such an observation should be corroborated with appropriate diagnostic patch testing.
Skin
The lotion contains isopropyl alcohol and may cause stinging or burning upon application to abraded or sun-burned skin.
If irritation or sensitization develops with the use of ELOCOM products, treatment should be discontinued and appropriate therapy instituted.
Prolonged use of topical corticosteroid preparations may produce striae or atrophy of the skin or subcutaneous tissue. Topical corticosteroids should be used with caution on lesions of the face, groin and axillae as these areas are more prone to atrophic changes than other areas of the body. Frequent observation is important if these areas are to be treated. If skin atrophy is observed, treatment should be discontinued.
7.1. Special Populations
7.1.1. Pregnancy
The safe use of topical corticosteroids during pregnancy has not been established. Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at dosage levels that are similar to therapeutic doses. Some corticosteroids have been shown to be teratogenic after dermal application in laboratory animals. The relevance of this finding to human beings has not been established.
In reproduction studies conducted in rats and rabbits, mometasone furoate produced effects such as reduced maternal body weight gain, suppression of fetal growth, delayed ossification, umbilical hernias, prolonged gestation, difficult and prolonged labor and inability to deliver (see 16. Non-Clinical Toxicology).
ELOCOM should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The minimum quantity should be used for the minimum duration.
7.1.2. Breastfeeding
Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. The safe use of topical corticosteroids during lactation has not been established. It is not known whether topical administration of corticosteroids could result in sufficient systemic absorption to produce detectable quantities in human milk. Because many drugs are excreted in human milk, caution should be exercised when ELOCOM is administered to a nursing woman. Administration of ELOCOM during lactation should only be considered if the expected benefit to the mother outweighs the risk to the infant. If used during lactation, ELOCOM should not be applied to the breasts to avoid accidental ingestion by the infant.
7.1.3. Pediatrics
Safety and efficacy of ELOCOM have not been established in pediatric patients.
Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of HPA axis suppression and Cushing’s syndrome when they are treated with topical corticosteroids. They are therefore also at greater risk of adrenal insufficiency during and/or after withdrawal of treatment.
Adverse effects including striae have been reported with use of topical corticosteroids in infants and children. HPA axis suppression, Cushing’s syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in children receiving topical corticosteroids. Manifestations of adrenal suppression in children include low plasma cortisol levels and an absence of response to ACTH stimulation. Manifestations of intracranial hypertension include bulging fontanelles, headaches, and bilateral papilledema. Chronic corticosteroid therapy may interfere with the growth and development of children.
7.1.4. Geriatrics
Safety of ELOCOM Lotion has not been established in geriatric patients. No overall differences in safety were observed between subjects greater than 65 years of age and younger subjects receiving ELOCOM Cream or Ointment. Topical corticosteroids should be used cautiously in elderly patients, reflecting their increased skin fragility and greater frequency of hepatic, renal, or cardiac dysfunction, and of concomitant disease or other drug therapy. Decreased hepatic or renal function in the elderly may delay elimination if systemic absorption occurs. The minimum quantity should be used for the minimum duration.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Local adverse reactions reported very rarely with ELOCOM Cream 0.1% include paresthesia, pruritus and signs of skin atrophy. In <1% of patients, local adverse reactions reported with ELOCOM Cream 0.1% include abscess, burning, disease exacerbation, dry skin, erythema, furunculosis and pimples.
Local adverse reactions rarely reported with ELOCOM Ointment 0.1% include burning, pruritus, tingling/stinging and signs of skin atrophy. In <1% of patients, adverse reactions reported with ELOCOM Ointment 0.1% include aggravated allergy, dermatitis, erythema, furunculosis, increased lesion size, nausea (one patient) and vaginal discharge (one patient).
Local adverse reactions rarely reported with ELOCOM Lotion 0.1% include burning, folliculitis, acneiform reaction, pruritus and signs of skin atrophy. In <1% of patients, adverse reactions reported with ELOCOM Lotion 0.1% include, papule, pustule and stinging.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Cream
The overall incidence of side effects was 1.6%, i.e. 5 of 319 subjects and patients reported treatment-related adverse experiences.
Ointment
The overall incidence of side effects was 4.9%, i.e. 40 of 812 subjects reported treatment-related adverse experiences.
Lotion
The overall incidence of side effects was 5.1%, i.e. 31 of 613 subjects and patients reported treatment-related adverse experiences.
Table 2 - Local Adverse Reactions Occurring at an Incidence ≥1% in Clinical Trials
Ointment n = 812 (%) | Lotion n = 457 (%) | |
Skin and subcutaneous tissue disorders Burning Pruritus Skin Atrophy | 1.6 1 1 | 2 - 1.3 (shininess, thinness, striae, telangiectasia) |
8.3. Less Common Clinical Trial Adverse Reactions
Cream
Skin and subcutaneous tissue disorders: skin burning sensation, pruritus, skin atrophy
Ointment
Infections and infestations: furuncle
Nervous system disorders: paraesthesia
Skin and subcutaneous tissue disorders: pain of skin
Lotion
Skin and subcutaneous tissue disorders: pruritus, dermatitis acneiform
The following local adverse reactions have been reported infrequently when other topical dermatologic corticosteroids have been used as recommended. These reactions are listed in an approximate decreasing order of occurrence: burning, itching, irritation, dryness, folliculitis, hypertrichosis, acneiform eruptions, hypopigmentation, perioral dermatitis, allergic contact dermatitis, maceration of the skin, secondary infection, skin atrophy, striae, miliaria.
Hypothalamic-pituitary-adrenal (HPA) axis suppression has been reported with topical corticosteroids. Manifestations of HPA axis suppression include increased weight / obesity, delayed weight gain / growth retardation in children, Cushing’s syndrome, cushingoid features (e.g., moon face, central obesity), HPA disorder, decreased endogenous cortisol levels, hyperglycemia / glucosuria, hypertension, osteoporosis, cataract, glaucoma, steroid withdrawal syndrome (see 7. Warnings and Precautions).
Systemic adverse reactions, such as vision blurred, have also been reported with the use of topical corticosteroids.
Posterior subcapsular cataracts have been reported following systemic use of corticosteroids.
9. Drug Interactions
9.3. Drug-Behavioural Interactions
Interaction with lifestyle has not been established.
9.4. Drug-Drug Interactions
Interactions with other drugs have not been established.
Table 3 - Established or Potential Drug-Drug Interactions
| [Proper/Common name] | Effect | Clinical comment |
| Drugs that can inhibit CYP3A4 (e.g., ritonavir, itraconazole) | Inhibit the metabolism of corticosteroids leading to increased systemic exposure | The extent to which this interaction is clinically relevant depends on the dose and route of administration of the corticosteroids and the potency of the CYP3A4 inhibitor. |
9.5. Drug-Food Interactions
Interaction with food has not been established.
9.6. Drug-Herb Interactions
Interaction with herbs has not been established.
9.7. Drug-Laboratory Test Interactions
Interaction with laboratory testing has not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
ELOCOM (mometasone furoate) has anti-inflammatory, antipruritic and vasoconstrictive actions. The exact mechanism, however, of corticosteroids in each disease is uncertain. Mometasone furoate, has been shown to have topical (dermatologic) and systemic pharmacologic and metabolic effects characteristic of this class of drugs.
10.2. Pharmacodynamics
No evidence of HPA axis suppression occurred in a study in which 15 g of mometasone furoate cream were applied BID for seven days to patients with psoriasis or atopic dermatitis. The cream was applied without occlusion to at least 30% of body surface.
In a study of the effects of mometasone furoate ointment on the HPA axis, 15 g were applied BID for seven days to patients with psoriasis or atopic dermatitis. The ointment was applied without occlusion to at least 30% of body surface. The results suggest that the drug caused a slight reduction of urinary-free cortisol. However, this change was not considered clinically important since it was not accompanied by subnormal levels of plasma cortisol or 17-OHC.
A special safety study demonstrated that mometasone furoate lotion 0.1% has minimal potential to cause skin irritation and/or sensitization reactions. Other safety data indicated that adverse reactions related to treatment with mometasone furoate lotion 0.1% were local in nature and similar to those commonly associated with topical corticosteroid therapy (see 14. Clinical Trials).
The pharmacologic profile of mometasone furoate was determined by standard laboratory methods. Relative to betamethasone valerate, the anti-inflammatory activity and anti-psoriatic activity of mometasone furoate were evaluated in mice and guinea pigs, respectively. Hypothalamic-pituitary-adrenal (HPA) axis suppression, thymolysis and skin atrophy were evaluated in mice.
In the croton oil assay in mice, mometasone furoate (ED50 = 0.02 µg/ear) was equipotent to betamethasone valerate after single application, and was approximately eight times as potent as betamethasone valerate after five daily applications (ED50 values = 0.002 µg/ear/day vs 0.014 µg/ear/day). In guinea pigs, mometasone furoate was approximately twice as potent as betamethasone valerate in reducing M. Ovalis-induced epidermal acanthosis after 14 daily applications.
With respect to pharmacologic activities commonly associated with corticosteroids, mometasone furoate (ED50 = 5.3 µg/ear/day) was less potent than betamethasone valerate (ED 50 = 3.1 µg /ear/day) in suppressing the HPA axis in mice after five daily applications. In the thymolysis assay, mometasone furoate (ED50 = 26.6 µg /ear/day) was approximately two times as potent as betamethasone valerate (ED50 = 51.6 µg /ear/day) when applied topically, and following subcutaneous administration for five days, mometasone furoate (ED50 = 11.2 µg /mouse) was approximately six times as potent as betamethasone valerate (ED50 = 59.8 µg /mouse. At doses five to 5000 times the effective anti-inflammatory doses, mometasone furoate was three to eight times more potent than betamethasone valerate with respect to skin thinning in mice. Based on the ratio of systemic potency (HPA suppression or thymolysis) to topical anti-inflammatory potency, the therapeutic indexes for mometasone furoate were approximately three to ten times greater than those for the comparative, betamethasone valerate. Therefore, mometasone furoate would be expected to have a superior safety margin to that of betamethasone valerate.
10.3. Pharmacokinetics
Cream
The percutaneous absorption of mometasone furoate cream 0.1% was evaluated in subjects receiving a single application of radio-labeled 3H-mometasone furoate cream 0.1% which remained on intact skin for eight hours. Based on the amount of radioactivity excreted in the urine and feces during the five-day study period, approximately 0.4% of the applied dose was absorbed systemically. The radioactive content found in plasma and red blood cells remained a few counts above background levels (corresponding to <0.1 ng/ml) throughout the study.
Ointment
A percutaneous absorption study with radio-labeled 3H-mometasone furoate ointment was conducted in adult male volunteers with intact skin. Based on the amounts of radioactivity excreted after an eight-hour application of the active ointment and analysis of urine and feces, approximately 0.7% of the applied dose was absorbed systemically without occlusion.
Lotion
Due to the occlusive nature of the ointment base, the percutaneous absorption following application of a corticosteroid ointment is greater than that of a topical corticosteroid in a cream or lotion formulation. Consequently, absorption following application of mometasone furoate lotion 0.1% is expected to be no greater than that which may occur after application of the ointment formulation.
The percutaneous absorption and excretion of 3H mometasone furoate cream and/or ointment was evaluated in rats, rabbits and dogs with doses ranging from 5.2 to 22 µg/cm2. Additionally, the tissue distribution of absorbed radioactivity was determined in rabbits.
Systemic absorption of 3H-mometasone furoate was minimal in all species studied, ranging from approximately 2% in dogs to 6% in rabbits over a 5 to 7-day period. The cream and ointment formulations were comparable with respect to systemic absorption. Plasma levels were low ranging from <0.1 to <1 ng/ml. Less than 1.3% of the applied dose was excreted in urine of all species and from 1.5 to 4.2% was excreted in feces. Characterization of urinary metabolites was not possible due to the low levels of drug in urine. However, it is well known that corticosteroids are metabolized to inactive water-soluble substances such as sulfate esters or glucuronides and are excreted as such. In rabbits, there was no unusual accumulation of radioactivity in any tissue.
11. Storage, Stability and Disposal
For ELOCOM Cream and Ointment, store between 15° and 30°C.
For ELOCOM Lotion, store between 15° and 25°C.
12. Special Handling Instructions
There are no special requirements for use or handling of this product.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: mometasone furoate
Chemical name: 9a,21-Dichloro-11b,17-dihydroxy-16a-methylpregna-1,4-diene-3,20-dione 17-(2-furoate)
Molecular formula and molecular mass: C27H30Cl2O6 and a molecular weight of 521.4
Structural formula:
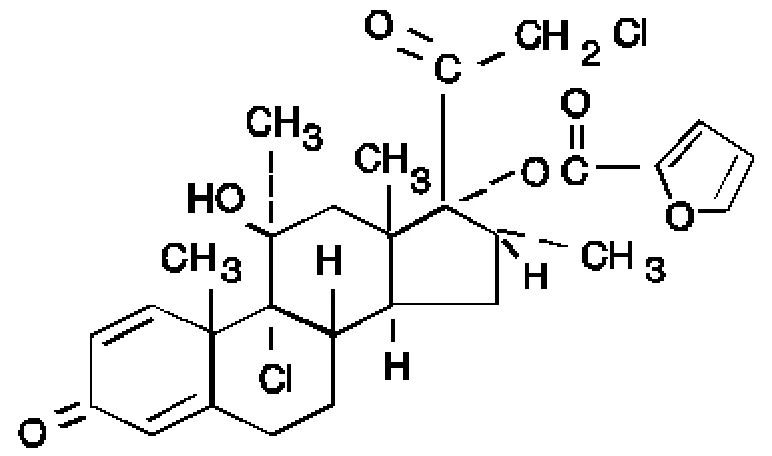
Physicochemical properties: Mometasone furoate is a white to off-white powder practically insoluble in water, slightly soluble in octanol and moderately soluble in ethyl alcohol.
14. Clinical Trials
Onset of Action:
Cream
Onset of action was investigated in several clinical trials with both pediatric and adult patients with various dermatologic conditions. A rapid onset of action with mometasone cream 0.1% was demonstrated after one week of treatment by percent improvement from baseline in total disease sign/symptom score (ranging from 25% to 81%). In these studies, percent improvement for the comparative agents were: betamethasone valerate (ranged from 43% to 81%); clobetasone butyrate (59%); hydrocortisone butyrate (54%); fluocinolone acetonide (24%); triamcinolone acetonide (36%); and for the vehicle alone (15% and 28%). Furthermore, in two of these studies, mometasone furoate cream 0.1% was significantly more effective than fluocinolone acetonide (P<0.001) and hydrocortisone butyrate (P<0.05) at Day 4 evaluation.
Ointment
Mometasone furoate ointment 0.1% QD also had a rapid onset of action in psoriatic patients as evidenced by percent improvement from baseline in total disease sign/symptom scores after one treatment week (ranging from 38% to 59%). Percent improvements for comparative agents were triamcinolone acetonide (28%), fluocinolone acetonide (33%), betamethasone dipropionate (23%), betamethasone valerate (56%) and vehicle alone (43%). In two of these studies mometasone furoate was significantly more effective than triamcinolone acetonide or fluocinolone acetonide at Day 4 evaluation (P<0.01).
The effects of mometasone furoate ointment 0.1% in the treatment of patients with atopic dermatitis also were rapid in onset as demonstrated by mean percent improvement and mean global evaluation scores at Day 4 and Week 1. Mometasone furoate-treated patients showed an improvement in total sign/symptom score that ranged from 27% to 47% at Day 4 and 51% to 64% at Week 1. In comparison, hydrocortisone butyrate and betamethasone valerate demonstrated 17% and 43% improvement, respectively, at Day 4 and 24% and 65%, respectively, at Week l. Global scores at one-week indicated moderate improvement in patients treated with mometasone furoate or betamethasone valerate and slight improvement in those treated with hydrocortisone butyrate.
Lotion
Mometasone furoate lotion 0.1% showed rapid onset of action after one treatment week in patients with scalp psoriasis. As demonstrated by results at Day 8 in one study, improvement in total sign/symptom scores was significantly (P<0.01) greater in mometasone-treated patients than in those treated with betamethasone valerate 0.1%.
Safety Studies:
No evidence of HPA axis suppression occurred in a study in which 15 g of mometasone furoate cream were applied BID for seven days to patients with psoriasis or atopic dermatitis. The cream was applied without occlusion to at least 30% of body surface. Plasma cortisol levels were within the lower limit of the normal range in these patients following application of the cream formulation.
In a study of the effects of mometasone furoate ointment on the HPA axis, 15 g were applied BID for seven days to patients with psoriasis or atopic dermatitis. The ointment was applied without occlusion to at least 30% of body surface. The results suggest that the drug caused a slight reduction of urinary-free cortisol. However, this change was not considered clinically important since it was not accompanied by subnormal levels of plasma cortisol or 17-OHC.
The results of other local and systemic safety studies also showed that mometasone furoate cream and ointment 0.1% have minimal percutaneous absorption and do not cause adrenal suppression. In other investigations, mometasone furoate cream and ointment 0.1% demonstrated minimal potential for irritation, sensitization, photocontact allergenicity and phototoxic reactions when used as recommended. Furthermore, when compared to hydrocortisone ointment 0.1% mometasone furoate ointment 0.1% has a low atrophogenic potential. No clinical meaningful changes in laboratory test values were observed with either mometasone furoate cream or ointment.
A special safety study to determine contact irritation and sensitization potential demonstrated that mometasone furoate lotion 0.1% has minimal potential to cause skin irritation and/or sensitization reactions. Doses of approximately 0.2 g of mometasone furoate lotion, mometasone lotion vehicle, betamethasone dipropionate lotion 0.05% betamethasone lotion vehicle, or USP white petrolatum were applied under occlusion for 48 to 72 hours, three times a week for three weeks (induction phase) to normal volunteers. Following a rest period, subjects were administered a challenge dose of two successive 48-hour applications to a previously untreated site. During the induction phase, irritation reactions to mometasone and one or more of the test preparations were observed in some subjects at isolated times. However, irritation reactions to mometasone were not uniform; they occurred at various times during the study but did not follow a specific pattern. Furthermore, no sensitization reactions occurred following the two successive challenge applications.
Other safety data indicated that adverse reactions related to treatment with mometasone furoate lotion 0.1% were local in nature and similar to those commonly associated with topical corticosteroid therapy. Evaluation of laboratory findings showed no indication of organ or organ system toxicity.
14.1. Clinical Trials by Indication
Psoriasis and Scalp Psoriasis
Efficacy Studies: Mometasone Furoate Cream 0.1%
A multicenter, double-blind, parallel-group study compared the efficacy of mometasone furoate cream 0.1% to that of its vehicle alone in patients with moderate to severe psoriasis. Mometasone furoate cream 0.1%, applied once a day (QD), was effective in ameliorating signs of psoriasis; it was significantly (P<0.01) more effective than the vehicle alone in reducing total disease sign score. After one week of treatment, improvement in the total disease sign scores averaged 25% for the mometasone-treated group and 15% for the vehicle-treated group, demonstrating a statistically significant (P<0.01) difference. After three weeks of treatment, a statistically significant (P<0.01) difference was again observed with the active cream. Improvement in total disease sign scores averaged 44% and 22% in the mometasone cream-and vehicle-treated patients, respectively. Results of the endpoint analysis also demonstrated that mometasone furoate was significantly (P<0.01) more effective than vehicle in reducing total disease sign scores. Furthermore, physician's global evaluation of overall change in disease status indicated significantly (P<0.01) greater improvement in the mometasone-treated patients compared to vehicle-treated patients at each evaluation over the entire three-week course of therapy.
In another two parallel-group, multicentric studies the efficacy of mometasone furoate cream 0.1% applied QD was compared to that of fluocinolone acetonide cream 0.025% applied three times daily (TID) for three weeks and to that of triamcinolone acetonide cream 0.1% applied twice daily (BID) for three weeks.
Based on improvement in total disease sign scores and physician's global evaluation of overall change in disease status in both studies, mometasone furoate cream 0.1% was significantly (P<0.01) more effective than fluocinolone acetonide and comparable to triamcinolone acetonide cream. Improvement in total disease sign scores, which ranged from 22% to 26%, was observed as early as Day 4 in mometasone furoate treated patients. Comparable improvement (22%) was seen in the triamcinolone-treated group.
In contrast, the fluocinolone-treated patients had achieved 16% improvement by Day 4. By study end, percent improvement ranged from 44% to 55% with mometasone furoate cream compared to 51% and 33% with triamcinolone and fluocinolone, respectively.
Mean global scores for mometasone furoate-treated patients also indicated continuous improvement over the treatment course. At the end of each study period, moderate improvement was observed in the mometasone furoate and triamcinolone acetonide treatment groups. Yet, little improvement was observed in the fluocinolone acetonide treatment group over the same period. Mean global scores in this group were never indicative of greater than slight improvement at any time during the study.
In a bilateral-paired comparative study, mometasone furoate cream 0.1% and betamethasone valerate cream 0.1%1 were applied BID for two weeks to psoriatic patients. While both study agents were equally effective in many patients, some patients responded better to mometasone therapy. Although at Day 4 lesions in more than one-half of patients had responded equally to either study preparation, most patients with differences in lesion response significantly favored treatment with mometasone furoate (P<0.03). By Day 15, total sign scores indicated that 56% of patients favored treatment with mometasone furoate as compared to 13% who favored treatment with betamethasone valerate and 31% of patients whose lesions responded equally to the two agents (P<0.01). Similarly, the physician's global evaluation scores at Day 15 indicated that lesions in 51% of patients responded more favorably to mometasone furoate cream as compared to lesions in 10% of patients who responded more favorably to betamethasone valerate cream (P<0.01). By treatment end, improvement in total disease sign scores averaged 59% in the mometasone-treated lesions and 49% in those treated with betamethasone valerate cream.
Efficacy Studies: Mometasone Furoate Ointment 0.1%
In two bilateral-paired comparison trials, the efficacy of BID applications of mometasone furoate ointment in concentrations of 0.1% and 0.05% was compared to that of betamethasone valerate ointment also applied BID for 14 days. Results showed that the 0.1% formulation of mometasone furoate ointment was significantly (P<0.05) more effective than betamethasone valerate ointment2. As demonstrated by the physician's global evaluation of change in disease status, 60% of patients responded more favorably to mometasone furoate ointment 0.1%, while 13% experienced a comparable response in the betamethasone valerate-treated group. Improvement from baseline in total disease sign score was 51% and 40% for mometasone furoate ointment 0.1% and betamethasone valerate ointment, respectively. Furthermore, these results also demonstrated that mometasone furoate ointment 0.05% was superior to betamethasone valerate ointment but not as effective as the 0.1% mometasone furoate ointment formulation.
In a third bilateral-paired comparative study of mometasone furoate ointment 0.1% and betamethasone dipropionate ointment3 applied BID for 14 days, percent improvement in total disease scores was similar between the two preparations, 63% and 58% for mometasone furoate ointment 0.1% and betamethasone dipropionate ointment, respectively. However, 38% of patients responded more favorably to mometasone furoate ointment 0.1% while 3% responded better to betamethasone dipropionate ointment.
Furthermore, three randomized, multicentric, parallel group studies were conducted in patients with psoriasis to compare the efficacy of mometasone furoate ointment 0.1% applied QD to that of triamcinolone acetonide4 applied BID, fluocinolone acetonide5 applied TID or to that of the vehicle alone applied QD for 21 days. Mometasone furoate ointment 0.1% was significantly (P<0.01) better than triacinolone acetonide, fluocinolone acetonide and the vehicle as demonstrated by the percent improvement in total disease sign scores. The superior efficacy of mometasone furoate ointment applied QD was observed despite the more frequent administrations of the two comparative agents. Physician’s global evaluation of disease status at endpoint analysis also confirmed that mometasone furoate ointment
1 VALISONE ® Cream
2 VALISONE ® Ointment
3 DIPROSONE ® Ointment
4 KENALOG® ER Squibb & Sons, Inc., Princeton, NJ USA
5 SYNALAR® Syntax Laboratories, Palo Alto, CA USA
0.1% was significantly (P<0.01) more effective than triamcinolone acetonide, fluocinolone acetonide or the vehicle alone in the treatment of patients with psoriasis.
Two additional studies in psoriatic patients compared QD applications of mometasone furoate ointment 0.1% with QD applications of betamethasone dipropionate 0.05% and BID applications of betamethasone valerate 0.1%6 respectively for three weeks. Mometasone furoate ointment 0.1% QD was significantly (P<0.01) more effective than betamethasone valerate BID and comparable to betamethasone dipropionate QD as demonstrated by percent improvement in total disease sign scores at endpoint analysis. Physician's overall evaluation of disease status also indicated that mometasone furoate ointment was significantly (P<0.01) more effective than betamethasone valerate in the treatment of psoriasis. At the end of the three-week study period, mean scores were indicative of marked to moderate improvement in most patients treated with mometasone furoate ointment. Comparable improvement was effected with betamethasone dipropionate and moderate to slight improvement was observed in the betamethasone valerate-treated group.
Efficacy Studies: Mometasone Furoate Lotion 0.1%
The efficacy of mometasone furoate lotion 0.1% in the treatment of patients with scalp psoriasis was evaluated in three randomized, parallel-group studies.
The first study compared QD application of mometasone furoate lotion 0.1% to that of the lotion vehicle alone. A second study compared mometasone furoate lotion 0.1% to betamethasone dipropionate lotion 0.05%7 both applied QD. In the third study, mometasone lotion 0.1% applied QD was compared to betamethasone valerate lotion 0.1%8 applied BID.
Results of these studies demonstrated that mometasone furoate lotion 0.1% was significantly (P<0.001) more effective than the vehicle and slightly superior in efficacy to betamethasone dipropionate and to betamethasone valerate applied QD and BID, respectively. Endpoint percent improvement in total sign/symptom scores ranged from 76% to 96% in the mometasone-treated groups and from 24% to 88% in the comparative groups. Endpoint analysis of physician's global evaluation also confirmed that mometasone-treated patients had significantly (P<0.02) greater improvement in overall disease status than patients treated with betamethasone dipropionate or vehicle alone.
Atopic Dermatitis and Seborrheic Dermatitis
Efficacy Studies: Mometasone Furoate Cream 0.1%
Another multicentric, double-blind, parallel-group study compared the efficacy of mometasone furoate cream 0.1% with that of its vehicle alone in patients with moderate to severe atopic dermatitis. Mometasone furoate cream applied QD was effective in ameliorating signs and symptoms of atopic dermatitis; it was significantly (P<0.01) more effective than vehicle alone. A rapid response to mometasone furoate was evident after seven treatment days when improvement in total disease sign/symptom scores averaged 50% and 28% in the mometasone cream and vehicle treatment groups, respectively, showing a statistically significant (P<0.01) difference. At Day 22, improvement in scores averaged 77% and 51% in the active cream- and vehicle treatment groups, respectively. Moreover, the endpoint analysis showed a 76% improvement in the mometasone cream-treated patients as compared to a 44% improvement in patients
6 BETNOVATE® Ointment, Glaxo Laboratories, UK
7 DIPROSONE® Lotion
8 BETNOVATE® Lotion, Glaxo Laboratories Limited, UK
treated with the vehicle. Physician's global evaluation scores indicated that patients treated with the active cream had significantly (P<0.01) greater improvement in disease status than vehicle-treated patients at each evaluation over the entire course of therapy.
In two single-blind studies, mometasone furoate cream 0.1% applied QD was compared to hydrocortisone butyrate cream 0.05%9 and to betamethasone valerate cream 0.1%10, each applied BID for three weeks.
Results in the first study demonstrated that mometasone furoate was significantly (P<0.05) more effective than hydrocortisone butyrate at all times during the study. At Day 4, percent improvement averaged 35% in the mometasone furoate-treated patients as compared to 30% in the hydrocortisone butyrate patient group. By Day 22, the average percent improvement was 88% and 84% in the mometasone- and hydrocortisone-treated groups, respectively.
Mean global scores for the mometasone-treated patients were indicative of moderate improvement as early as Day 4, while only slight improvement was observed in the hydrocortisone group.
In the second study, the extent of improvement in mometasone furoate-treated patients was similar to that observed in other studies; comparable improvement was seen in the betamethasone-treated group. By Day 4, patients in both treatment groups showed approximately 40% improvement which progressed throughout the study. At the end of the study period, mean global scores in both treatment groups were indicative of marked improvement.
Efficacy Studies: Mometasone Furoate Ointment 0.1%
Patients with atopic dermatitis participated in a bilateral-paired comparative study, which evaluated the efficacy of mometasone furoate ointment 0.1% against that of betamethasone valerate ointment. Results demonstrated that mometasone furoate ointment 0.1% was equivalent in activity to betamethasone valerate ointment when both agents were applied BID. Another three randomized, multicentric parallel-group studies compared the efficacy of mometasone furoate ointment 0.1% QD with that of betamethasone valerate ointment BID, the ointment vehicle alone applied QD, or hydrocortisone butyrate ointment 0.1%11 applied BID for three weeks. In these studies, mometasone furoate was equivalent to the known standard agents, betamethasone valerate and hydrocortisone butyrate, even though mometasone furoate was applied less frequently than each of these comparatives. Percent improvement in total disease sign score at end-point analysis in the three studies were 82%, 83% and 60%, respectively, for mometasone furoate ointment 0.1% as compared to 79%, 24% and 46% for betamethasone valerate ointment, the vehicle and hydrocortisone butyrate, respectively (P<0.01). Furthermore, global scores at endpoint reflected marked improvement in the mometasone furoate and betamethasone valerate-treatment groups, moderate improvement in the hydrocortisone-treated group and slight improvement in the vehicle-treated group.
Efficacy Studies: Mometasone Furoate Lotion 0.1%
Two parallel-group studies in patients with seborrheic dermatitis compared the efficacy of QD application of mometasone furoate lotion 0.1% to that of the lotion vehicle alone and to that of betamethasone valerate lotion 0.1% applied BID. In these studies, mometasone furoate was significantly (P<0.001) more effective than the vehicle and comparable in efficacy to betamethasone valerate lotion. Endpoint percent
9 LOCOID® Cream, Owen Laboratories, S.A. TX, USA
10 BETNOVATE® Cream, Glaxo Laboratories Limited, UK
11 LOCOID® Ointment, Owen Laboratories, SA TX USA
improvement in total sign/symptom scores was 86% and 89% in the mometasone-treated groups compared to 53% and 87%, in the vehicle and comparative groups, respectively. Similarly, endpoint mean global scores reflected marked improvement in the mometasone and betamethasone valerate-treated patients and slight improvement in the vehicle.
Corticosteroid-Responsive Dermatoses
Efficacy Studies: Mometasone Furoate Cream 0.1%
The efficacy of mometasone furoate cream 0.1% applied QD was compared to that of betamethasone valerate cream 0.1%12 applied BID in the treatment of various corticosteroid- responsive dermatoses. Mometasone furoate cream QD was as effective as betamethasone valerate applied BID as indicated by percent improvement in total disease sign/ symptoms scores and physician's global evaluation of overall change in disease status. Onset of action was rapid with both preparations, and progressive improvement occurred in both treatment groups throughout the three-week study period. By Day 22, percent improvement averaged 94% and 97% in the mometasone- and betamethasone-treated patients, respectively. Mean global scores for both treatment groups were indicative of moderate improvement as early as Day 4. At study end, mean global scores in the mometasone and betamethasone groups indicated complete clearing of lesions in most patients in each treatment group.
Corticosteroid-Responsive Dermatoses in Pediatric Patients
Two randomized, parallel-group studies evaluated the efficacy of mometasone furoate cream 0.1% in the treatment of various corticosteroid-responsive dermatoses in pediatric patients.
In the first study, mometasone furoate cream 0.1% applied QD was compared to clobetasone butyrate cream 0.05%13 applied BID for three weeks. In the second study, mometasone furoate cream 0.1% applied QD was compared to betamethasone valerate cream 0.1% applied BID for three weeks.
Results of both studies demonstrated that daily single applications of mometasone furoate cream 0.1% were as effective as clobetasone 0.05% and betamethasone 0.1% each applied twice daily in ameliorating signs/symptoms of corticosteroid-responsive dermatoses. With mometasone furoate cream, symptomatic improvement was observed as early as Day 4 and ranged from 36% to 46%. Similarly, 28% improvement occurred with clobetasone butyrate cream and 52% with betamethasone valerate cream. At Day 22, percent improvement ranged from 94% to 99% with mometasone furoate cream and was 90% and 94% with clobetasone and betamethasone, respectively. Mean global scores in all treatment groups were indicative of rapid, progressive improvement in disease status throughout the study. At study end, mean global scores indicated complete clearing to marked improvement in most mometasone-treated patients, complete clearing in the betamethasone-treated patients, and marked improvement in the clobetasone group.
Efficacy Studies: Mometasone Furoate Ointment 0.1%
In three parallel-group studies, the efficacy of mometasone furoate ointment 0.1% was compared to that of betamethasone valerate 0.05% and clobetasone butyrate 0.025%i in the treatment of various corticosteroid-responsive dermatoses. Mometasone furoate ointment was applied QD while the
12 VALISONE ® Cream
13 EUMOVATE ® Cream
comparative agents were each applied BID for three weeks. After one treatment week, improvement in disease signs ranged from 58% to 90% with QD mometasone furoate administration, 52% to 77% with BID application of betamethasone valerate and 69% with BID administration of clobetasone butyrate. By treatment end, percent improvement averaged 93% for mometasone furoate, 89% and 93% for betamethasone valerate and 90% for clobetasone butyrate. At endpoint evaluation, global scores indicated disease clearance in the majority of mometasone-treated patients; marked improvement was observed in most patients treated with betamethasone valerate or clobetasone butyrate.
16. Non-Clinical Toxicology
General Toxicology:
A program consisting of evaluation of local and systemic toxicity, reproductive toxicity, genetic toxicity, dermal irritation and sensitization potential and ocular irritation was conducted to determine the safety of mometasone furoate cream and ointment. Acute toxicity was evaluated in mice, rats and dogs including young (21-day old) mice and rats. Repeated dose toxicity was evaluated in rats, rabbits and dogs by subcutaneous and/or topical routes. Reproduction studies were conducted in rats and rabbits and included evaluation of teratology, peri and post- natal development and general reproductive performance. Sensitization potential was determined in guinea pigs and dermal and ocular irritation were evaluated in rabbits. In vitro and in vivo genetic toxicology studies were conducted to evaluate potential mutagenicity and clastogenicity (capacity to induce chromosomal changes).
The acute subcutaneous LD50 values of mometasone furoate were determined to be between 200 and 2000 mg/kg in mice, 2000 mg/kg or greater in rats and >200 mg/kg in dogs. Following oral administration the LD50 values were >2000 mg/kg in mice and rats. As expected, the LD50 values for young (21-day old) mice and rats were 2 to 20 times lower than those for adult animals.
Following repeated administration of mometasone furoate in rats, rabbits and dogs at doses up to 670 times the anticipated maximum human dose for up to 6 months, findings were typical of corticosteroid administration in all species. These included (1) slight reduction in body weight gain, (2) skeletal muscle wasting, (3) abdominal distention, (4) decrease in lymphocytes and eosinophils and increase in neutrophils, (5) increase in serum transaminases (ALT and AST), cholesterol and triglycerides, (6) lipemia, and (7) organ changes (atrophy of spleen and thymus, local skin thinning, increased liver and kidney weights and reduced osteogenesis). These changes were generally observed more frequently or more severe in animals receiving the comparative agent, betamethasone valerate. No unusual systemic effects were observed with either drug. Dermal responses to repeated application of mometasone furoate or betamethasone valerate cream were limited to transient episodes of slight to moderate erythema, skin wrinkling, desquamation and the presence of papules and/or pustules.
Following repeated topical application in rabbits for ten days, the dermal response to mometasone furoate cream was minimal and characterized by very slight erythema, the occasional appearance of papules, atonia, desquamation and wrinkling. Mometasone furoate was not a sensitizer in guinea pigs and was not significantly irritating to the eyes of rabbits.
Genotoxicity:
In genetic toxicity studies, mometasone furoate was not mutagenic in bacteria (Ames test) or mammalian (mouse lymphoma) cells and was not clastogenic in the mouse micronucleus test.
Reproductive and Developmental Toxicology:
In reproduction studies, mometasone furoate produced effects which are known to be associated with corticosteroids and/or progestational agents such as reduced maternal body weight gain, suppression of fetal growth, delayed ossification, umbilical hernias, prolonged gestation, difficult and prolonged labor and inability to deliver.