


Product Monograph - Esbriet (Hoffmann-la Roche, 267 mg, 801 mg)
RECENT MAJOR LABEL CHANGES
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | [11/2023] |
|---|---|
| 7 Warnings and Precautions | [11/2023] |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1. Pediatrics ................................................................................................................ 4
1.2. Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1. Dosing Considerations ............................................................................................ 5
4.2. Recommended Dose and Dosage Adjustment ....................................................... 5
4.3. Reconstitution ........................................................................................................ 7
4.4. Administration ........................................................................................................ 7
4.5. Missed Dose ........................................................................................................... 7
5 OVERDOSAGE .............................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 8
7 WARNINGS AND PRECAUTIONS .................................................................................. 9
7.1. Special Populations............................................................................................... 11
7.1.1. Pregnant Women ........................................................................................... 11
7.1.2. Breast-feeding ................................................................................................ 12
7.1.3. Pediatrics ........................................................................................................ 12
7.1.4. Geriatrics ........................................................................................................ 12
8 ADVERSE REACTIONS ................................................................................................ 12
8.1. Adverse Reaction Overview .................................................................................. 12
8.2. Clinical Trial Adverse Reactions ............................................................................ 12
8.2.1. Clinical Trial Adverse Reactions - Pediatrics .................................................... 15
8.3. Less Common Clinical Trial Adverse Reactions ..................................................... 15
8.3.1. Less Common Clinical Trial Adverse Reactions - Pediatrics ............................. 15
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 15
8.5. Post-Market Adverse Reactions ........................................................................... 16
9 DRUG INTERACTIONS ................................................................................................ 17
9.1. Serious Drug Interactions ..................................................................................... 17
9.2. Drug Interactions Overview .................................................................................. 18
9.3. Drug-Behavioural Interactions .............................................................................. 18
9.4. Drug-Drug Interactions ......................................................................................... 18
9.5. Drug-Food Interactions ......................................................................................... 19
9.6. Drug-Herb Interactions ......................................................................................... 20
9.7. Drug-Laboratory Test Interactions ........................................................................ 20
10 CLINICAL PHARMACOLOGY ....................................................................................... 20
10.1. Mechanism of Action ...................................................................................... 20
10.2. Pharmacodynamics ........................................................................................ 20
10.3. Pharmacokinetics ........................................................................................... 21
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 24
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 24
PART II: SCIENTIFIC INFORMATION ....................................................................................... 25
13 PHARMACEUTICAL INFORMATION ............................................................................ 25
14 CLINICAL TRIALS ........................................................................................................ 25
14.1. Clinical Trials by Indication ............................................................................. 25
Idiopathic Pulmonary Fibrosis ........................................................................................ 25
14.2. Comparative Bioavailability Studies ................................................................ 29
14.3. Immunogenicity .............................................................................................. 30
15 MICROBIOLOGY ........................................................................................................ 30
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 30
PATIENT MEDICATION INFORMATION .................................................................................. 36
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
ESBRIET® (pirfenidone) is indicated for treatment of idiopathic pulmonary fibrosis (IPF) in adults.
1.1. Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of ESBRIET in pediatric patients have not been established.
1.2. Geriatrics
No dose adjustment is necessary in patients 65 years and older (see 10 CLINICAL PHARMACOLOGY).
2 CONTRAINDICATIONS
- Hypersensitivity to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the product monograph.
- History of angioedema with pirfenidone (see 7 WARNINGS AND PRECAUTIONS).
- Concomitant use of fluvoxamine (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
- Severe hepatic impairment or end-stage liver disease (see 7 WARNINGS AND PRECAUTIONS).
- Severe renal impairment (CrCl <30 mL/min) or end stage renal disease requiring dialysis (see 7 WARNINGS AND PRECAUTIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Drug Interactions with Inhibitors of CYP1A2 and Other CYP Isoenzymes Fluvoxamine ESBRIET is contraindicated in patients with concomitant use of fluvoxamine (a strong inhibitor of CYP1A2 with inhibitory effects on CYP2C9, 2C19, and 2D6). Fluvoxamine should be discontinued prior to the initiation of treatment with ESBRIET and avoided during ESBRIET therapy due to the potential for reduced clearance of pirfenidone (see 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS). Ciprofloxacin Co-administration of ESBRIET and 750 mg of ciprofloxacin (a moderate and selective inhibitor of CYP1A2) increased the exposure to pirfenidone by 81%. If ciprofloxacin at the dose of 750 mg twice daily (a total daily dose of 1500 mg) cannot be avoided, the dose of ESBRIET should be reduced to 1602 mg daily (a dose of 534 mg, three times a day). ESBRIET should be used with caution when ciprofloxacin is used at a total daily dose of 250 to 1000 mg (see 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS). |
|---|
Strong and Selective Inhibitors of CYP1A2 In vitro-in vivo extrapolations indicate that strong and selective inhibitors of CYP1A2 have the potential to increase the exposure to pirfenidone by approximately 2 to 4-fold. If concomitant use of ESBRIET with a strong and selective inhibitor of CYP1A2 cannot be avoided, the dose of ESBRIET should be reduced to 801 mg daily (267 mg, three times a day). Patients should be closely monitored for emergence of adverse reactions associated with ESBRIET therapy. Discontinue ESBRIET if necessary (see 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS). Other CYP1A2 Inhibitors Agents or combinations of agents that are moderate to strong inhibitors of both CYP1A2 and one or more other CYP isoenzymes involved in the metabolism of pirfenidone (i.e., CYP2C9, 2C19, 2D6, and 2E1) should be avoided during ESBRIET treatment. ESBRIET should be used with caution in patients treated with moderate inhibitors of CYP1A2 that do not inhibit other CYP isoenzymes (see 9 DRUG INTERACTIONS). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1. Dosing Considerations
- Treatment with ESBRIET should be initiated and supervised by specialist physicians experienced in the diagnosis and treatment of IPF.
- ESBRIET should be taken with food (see 9 DRUG INTERACTIONS).
- ESBRIET should not be taken concomitantly with fluvoxamine (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
- Reduction of the ESBRIET dose may be required for ciprofloxacin and strong but selective inhibitors of CYP1A2 (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
4.2. Recommended Dose and Dosage Adjustment
Adults
The recommended daily dose of ESBRIET for patients with IPF is 801 mg three times a day with food, for a total dose of 2403 mg/day.
Upon initiating treatment, the dose should be titrated to the recommended daily dose of 2403 mg/ day over a 14-day period to improve tolerability as follows:
Days 1 to 7: a dose of 267 mg administered, three times a day (801 mg/day) with food
Days 8 to 14: a dose of 534 mg administered, three times a day (1602 mg/day) with food
Day 15 onward: a dose of 801 mg administered, three times a day (2403 mg/day) with food
Doses above 2403 mg/day are not recommended for any patient (see 5 OVERDOSAGE).
Patients who miss 14 consecutive days or more of ESBRIET treatment should re-initiate therapy by undergoing the initial 2 week titration regimen up to the recommended daily dose.
If treatment is interrupted for less than 14 consecutive days, the dose can be resumed at the previous recommended daily dose without titration.
Dose Adjustments
Gastrointestinal Events: In patients who experience intolerance to therapy due to gastrointestinal side effects, patients should be reminded to take ESBRIET with food. If gastrointestinal events do not improve, or worsen in severity, dose reduction or discontinuation of ESBRIET may be warranted. The dose of ESBRIET may be reduced to 267 mg – 534 mg, two to three times a day with food with re-escalation to the recommended daily dose as tolerated.
Photosensitivity Reaction or Rash: Patients who experience a mild to moderate photosensitivity reaction or rash should be reminded to use a sunblock daily and to avoid exposure to the sun. The dose of ESBRIET may be reduced to 801 mg each day. If the rash persists after 7 days, ESBRIET should be discontinued for 15 days, with re-escalation to the recommended daily dose in the same manner as the dose escalation period.
Patients who experience severe photosensitivity reaction or rash should be instructed to discontinue ESBRIET promptly and to seek medical advice without delay (see 7 WARNINGS AND PRECAUTIONS). Once the rash has resolved, ESBRIET may be re-introduced and re escalated up to the recommended daily dose at the discretion of the physician.
Ciprofloxacin: Co-administration of ESBRIET and 750 mg of ciprofloxacin (a moderate and selective inhibitor of CYP1A2) increased the exposure to pirfenidone by 81%. If ciprofloxacin at the dose of 750 mg twice daily (a total daily dose of 1500 mg) cannot be avoided, the dose of ESBRIET should be reduced to 1602 mg daily (a dose of 534 mg, three times a day). ESBRIET should be used with caution when ciprofloxacin is used at a total daily dose of 250 to 1000 mg (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
Geriatrics: No dose adjustment is necessary in patients 65 years and older.
Pediatrics: ESBRIET has not been studied in pediatric patients, and is not recommended for use in this patient population.
Hepatic Impairment: No dose adjustment is necessary in patients with mild to moderate hepatic impairment (i.e., Child-Pugh Class A and B). However, since plasma levels of pirfenidone may be increased in individuals with moderate hepatic impairment (around 60% increase in Child-Pugh Class B), patients should be monitored closely for signs of toxicity especially if they are concomitantly taking a known CYP1A2 inhibitor (see 9 DRUG INTERACTIONS). ESBRIET should not be used in patients with severe hepatic impairment or end-stage liver disease (see 2 CONTRAINDICATIONS). Liver chemistry tests (ALT, AST, bilirubin) should be monitored before and during treatment with ESBRIET. Dose adjustments, including discontinuation, may be necessary in the event of elevations in ALT, AST, and/or bilirubin (see 7 WARNINGS AND PRECAUTIONS, and see below for dose adjustments).
Recommendations in Case of ALT, AST, Bilirubin Elevations
If a patient exhibits a Grade 2 ALT and/or AST elevation to >3 to <5 × ULN without hyperbilirubinaemia after starting treatment with ESBRIET at the recommended dose of 2403 mg/day, or any time after starting therapy, other causes should be excluded, and the patient monitored closely. Discontinuation of other medicines associated with liver toxicity should be considered. If clinically appropriate, the dose of ESBRIET should be reduced or interrupted. Once ALT and AST levels have resolved, ESBRIET may be re-escalated to the recommended daily dose and continued, if tolerated and the patient should be monitored closely.
If a patient exhibits any ALT and/or AST elevation to >3 to <5 × ULN accompanied by clinical signs or symptoms indicative of liver injury or accompanied by hyperbilirubinaemia (excluding patients with known predominantly unconjugated hyperbilirubinaemia, e.g., Gilbert’s syndrome), ESBRIET should be discontinued promptly. The patient should be monitored closely until resolution of elevated ALT, AST, bilirubin, and symptoms. The patient should NOT be re-challenged with ESBRIET.
If a patient exhibits ALT and/or AST elevation to ≥5 × ULN regardless of the level of serum bilirubin, ESBRIET should be discontinued promptly and the patient monitored closely until resolution of elevated ALT, AST, and bilirubin. The patient should NOT be re-challenged with ESBRIET.
Renal Impairment: No dose adjustment is necessary in patients with mild to moderate renal impairment. ESBRIET should not be used in patients with severe renal impairment or end-stage renal disease requiring dialysis (CrCl <30mL/min, per Cockcroft-Gault equation) (see 2 CONTRAINDICATIONS).
Severe cutaneous adverse reactions (SCARs): If patients experience severe cutaneous adverse reactions (SCARs), consider immediate withdrawal of ESBRIET to allow for resolution of symptoms. If a SCAR is confirmed, Esbriet must not be restarted and should be permanently discontinued.
4.3. Reconstitution
Not applicable.
4.4. Administration
ESBRIET is to be swallowed whole with water and taken with food to reduce the possibility of nausea or dizziness.
4.5. Missed Dose
If a dose is missed, the next dose should be taken as originally planned. Double doses should not be taken to make up for forgotten doses. If doses are missed for more than 14 days, ESBRIET treatment should be re-initiated by undergoing the initial 2 week titration regimen up to the recommended daily dose.
5 OVERDOSAGE
In studies PIPF-004 and PIPF-006, an overdose was defined as any study drug exposure of greater than 15 capsules (>4005 mg) in any given day or greater than 5 capsules (>1335 mg) in any single dose. No patients met the definition of overdose in these studies. There is therefore, limited clinical experience with overdose. Multiple doses of pirfenidone up to a total dose of 4806 mg/day were administered as six 267 mg capsules three times daily to healthy adult volunteers over a 12-day dose escalation period. Adverse reactions were generally consistent with the most frequently reported adverse reactions for pirfenidone.
There is no specific antidote. In the event of a suspected overdose, supportive medical care should be provided including monitoring of vital signs and close observation of the clinical status of the patient.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 Dosage Forms, Strengths, Composition and Packaging
ESBRIET capsules are supplied in 250 mL white high-density polyethylene (HDPE) bottle with child-resistant closure containing 270 capsules, or in treatment packs as follows:
2-week treatment initiation pack
7 x PVC/PE/PCTFE aluminium foil blister strips, each containing 3 capsules (for the Week 1 dosing), packaged together with 7 x PVC/PE/PCTFE aluminium foil blister strips, each containing 6 capsules (for the Week 2 dosing), for a total of 63 capsules per pack.
ESBRIET tablets are supplied in HDPE bottle(s) with child- resistant closures in the following packaging formats:
267 mg
Carton containing one bottle with 21 tablets, 42 tablets or 270 tablets
801 mg
Carton containing one bottle with 90 tablets
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | capsule 267 mg Hard gelatin two-piece capsules have a white to off-white opaque body and white to off-white opaque cap imprinted with “PFD 267 mg” in brown ink and containing a white to pale yellow powder | Each capsule contains pirfenidone and the following non-medicinal ingredients: microcrystalline cellulose, croscarmellose sodium, povidone, and magnesium stearate. In addition, the capsule shell contains gelatin and titanium dioxide. The capsule brown printing ink includes shellac, iron oxide black, iron oxide red, iron oxide yellow, propylene glycol, ammonium hydroxide. |
| oral | tablet 267 mg tablet 801 mg Film-coated tablets are oval, biconvex, debossed with “PFD”, containing 267 mg (yellow), and 801 mg (brown) pirfenidone | Each tablet contains pirfenidone and the following non-medicinal ingredients: colloidal anhydrous silica, croscarmellose sodium, iron oxide, macrogol (polyethylene glycol), magnesium stearate, microcrystalline cellulose, polyvinyl alcohol, povidone, talc, and titanium dioxide. |
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Treatment with ESBRIET should be initiated and supervised by specialist physicians experienced in the diagnosis and treatment of IPF.
ESBRIET should be taken with food to reduce the incidence of dizziness or nausea.
Physicians should monitor patients as frequently as clinically indicated for toxicities and for any additional medication used to treat the patient (see 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS). For significant side effects, the treatment of symptoms and dose reduction or discontinuation of ESBRIET should be considered.
Carcinogenesis and Mutagenesis
Only animal data is available, see 16 NON-CLINICAL TOXICOLOGY.
Driving and Operating Machinery
ESBRIET may cause dizziness and fatigue, which could influence the ability to drive or use machines. Patients should be reminded to take ESBRIET with food to reduce the incidence of dizziness. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Fatigue Fatigue has been reported in patients treated with ESBRIET. Therefore, patients should know how they react to ESBRIET before they engage in activities requiring mental alertness or coordination (e.g., driving or using machinery). If fatigue does not improve or if it worsens in severity, dose reduction or discontinuation of pirfenidone may be warranted.
Gastrointestinal
Gastrointestinal events (e.g., nausea, diarrhoea, dyspepsia, vomiting) have been reported in patients treated with ESBRIET. Patients who experience gastrointestinal side effects should be reminded to take ESBRIET with food. If gastrointestinal events do not improve or worsen in severity, dose reduction or discontinuation of ESBRIET may be warranted (see 4 DOSAGE AND ADMINISTRATION).
Hepatic/Biliary/Pancreatic
Drug-Induced Liver Injury (DILI) in the form of transient and clinically silent elevations in transaminases has been commonly reported in patients treated with ESBRIET. Uncommonly, these elevations were associated with concomitant bilirubin increases, and serious clinical consequences including isolated cases with fatal outcome have been reported post-marketing (see 8 ADVERSE REACTIONS, Post-Market Adverse Reactions). Liver chemistry tests (ALT, AST, and bilirubin) should be performed prior to the initiation of treatment with ESBRIET, and subsequently at monthly intervals for the first 6 months and then every 3 months thereafter. In addition, liver function tests should be promptly measured in patients who report symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice. In the event of elevations of ALT and/or AST, or clinical signs and symptoms of liver injury, the dose of ESBRIET may need to be reduced or treatment discontinued (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 4 DOSAGE AND ADMINISTRATION, Recommendations in Case of ALT, AST, Bilirubin Elevations).
In patients with moderate hepatic impairment (i.e., Child-Pugh Class B), ESBRIET exposure was increased by 60%. ESBRIET should be used with caution in patients with pre-existing mild to moderate hepatic impairment (i.e., Child-Pugh Class A and B) given the potential for increased ESBRIET exposure. Patients should be monitored closely for signs of toxicity especially if they are concomitantly taking a known CYP1A2 inhibitor (see 9 DRUG INTERACTIONSand10 CLINICAL PHARMACOLOGY). ESBRIET has not been studied in individuals with severe hepatic impairment. ESBRIET should not be used in patients with severe hepatic impairment or end-stage liver disease (see 2 CONTRAINDICATIONS).
Immune
Angioedema
Reports of angioedema (some serious) such as swelling of the face, lips and/or tongue which may be associated with difficulty breathing or wheezing have been received in association with use of ESBRIET in the post-marketing setting. Therefore, patients who develop signs or symptoms of angioedema following administration of ESBRIET should immediately discontinue treatment. Patients with angioedema should be managed according to standard of care. ESBRIET should not be used in patients with a history of angioedema due to ESBRIET (see 2 CONTRAINDICATIONS).
Monitoring and Laboratory Tests
Liver chemistry tests (ALT, AST and bilirubin) should be performed prior to the initiation of treatment with ESBRIET, and subsequently at monthly intervals for the first 6 months and then every 3 months thereafter. In addition, liver function tests should be promptly measured in patients who report symptoms that may indicate livery injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice. In the event of elevation in ALT, AST and/or bilirubin or clinical signs and symptoms of liver injury, the dose of ESBRIET may need to be reduced or treatment discontinued (see 4 DOSAGE AND ADMINISTRATION: Recommendations in case of elevations in ALT, AST, bilirubin).
If a patient exhibits any ALT and/or AST elevation accompanied by clinical signs and symptoms of liver injury or accompanied by hyperbilirubinaemia, ESBRIET should be discontinued promptly. The patient should be monitored closely until resolution of elevated ALT, AST and bilirubin and symptoms. The patient should NOT be re-challenged with ESBRIET.
If a patient exhibits ALT and/or AST elevation to ≥5 × ULN regardless of the level of serum bilirubin, ESBRIET should be discontinued promptly and the patient monitored closely until resolution of ALT and AST. The patient should NOT be re-challenged with ESBRIET.
Neurologic
Dizziness
Dizziness has been reported in patients treated with ESBRIET. Therefore, patients should know how they react to ESBRIET before they engage in activities requiring mental alertness or coordination (e.g., driving or using machinery). Patients who experience intolerance to therapy due to dizziness should be reminded to take ESBRIET with food to reduce dizziness. If dizziness does not improve or worsens in severity, dose adjustment or discontinuation of ESBRIET may be warranted.
Renal
ESBRIET should not be used in patients with severe renal impairment, or end-stage renal disease requiring dialysis (CrCl <30 mL/min, per Cockcroft-Gault equation) (see 2 CONTRAINDICATIONS). ESBRIET should be used with caution in patients with mild (CrCl 51-80 mL/min) and moderate renal impairment (CrCl 30-50 mL/min) (see 10 CLINICAL PHARMACOLOGY- Renal Insufficiency).
Reproductive Health: Female and Male Potential Fertility
No adverse effects on fertility were observed in preclinical studies (see 16 NON-CLINICAL TOXICOLOGY).
Skin
Photosensitivity Reaction and Rash Photosensitivity reaction and rash have been reported in patients treated with ESBRIET.
Patients treated with ESBRIET should be advised to avoid or minimize exposure to direct and indirect sunlight, including through windows and from sunlamps, and to avoid other medicinal products known to cause photosensitivity. Patients should be instructed to use daily an effective sun block (at least SPF 50 against UVA and UVB), and to wear clothing that protects against sun exposure such as wide-brimmed hats and long sleeves. Patients should be instructed to report promptly to their physician symptoms of photosensitivity reaction or rash. Severe photosensitivity reactions are uncommon. Dose reduction and temporary treatment discontinuation may be necessary in the event of photosensitivity reaction or rash. ESBRIET may be reintroduced with re-escalation to the tolerated dose in the same manner as the dose-escalation period (see 4 DOSAGE AND ADMINISTRATION).
Severe Cutaneous Adverse Reactions
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS), which can be life-threatening or fatal, have been reported post-marketing in association with the use of ESBRIET. If signs or symptoms of SCARs occur, ESBRIET should be withdrawn immediately. If the patient has developed SJS or TEN or DRESS with the use of ESBRIET, treatment with ESBRIET must not be restarted and should be permanently discontinued.
Weight Loss Decreased appetite and weight loss have been reported in patients treated with ESBRIET. Physicians should monitor patients’ weight, and when appropriate, encourage increased caloric intake if weight loss is considered to be of clinical significance.
7.1. Special Populations
7.1.1. Pregnant Women
ESBRIET has not been studied in pregnant women. In animals, placental transfer of pirfenidone and/or its metabolites to the foetus occurs with the potential for accumulation of pirfenidone and/or its metabolites in amniotic fluid.
At high doses (≥1000 mg/kg/day) rats exhibited prolongation of gestation and reduction in foetal viability.
The use of ESBRIET should be avoided during pregnancy.
7.1.2. Breast-feeding
It is unknown whether pirfenidone or its metabolites are excreted in human milk. Available pharmacokinetic data in animals have shown rapid excretion of pirfenidone and/or its metabolites in milk with the potential for accumulation of pirfenidone and/or its metabolites in milk (see 16 NON-CLINICAL TOXICOLOGY). A risk to the breast-fed child cannot be excluded.
A decision must be made whether to discontinue breast-feeding or to discontinue ESBRIET therapy, taking into account the benefits of breast-feeding for the child and of ESBRIET therapy for the mother.
7.1.3. Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of ESBRIET in pediatric patients have not been established.
7.1.4. Geriatrics
No dose adjustment is necessary in patients 65 years and older (see 10 CLINICAL PHARMACOLOGY).
8 ADVERSE REACTIONS
8.1. Adverse Reaction Overview
The safety of pirfenidone has been evaluated in more than 1400 subjects with over 170 subjects exposed to pirfenidone for more than 5 years in clinical trials.
The most common adverse reactions (≥10%) are nausea, rash, abdominal pain, upper respiratory tract infection, diarrhea, fatigue, headache, dyspepsia, dizziness, vomiting, decreased appetite, gastro-esophageal reflux disease, sinusitis, insomnia, weight decreased, and arthralgia.
At the recommended dosage of 2403 mg/day, 14.6% of patients on ESBRIET capsules compared to 9.6% on placebo permanently discontinued treatment because of an adverse event and 42.7% of patients on ESBRIET capsules compared to 16.2% on placebo had a dose interruption or reduction because of an adverse event. The most common (>1%) adverse reactions leading to discontinuation were rash and nausea. The most common (>3%) adverse reactions leading to dosage reduction or interruption were rash, nausea, diarrhea, and photosensitivity reaction.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
ESBRIET capsules was studied in 3 randomized, double-blind, placebo-controlled trials (Studies PIPF-016, PIPF-004 and PIPF-006) in which a total of 623 patients received 2403 mg/day of ESBRIET capsules and 624 patients received placebo. Subjects ages ranged from 40 to 80 years (mean age of 67 years).
Most patients were male (74%) and Caucasian (95%). The mean duration of exposure to ESBRIET capsules was 62 weeks (range: 2 to 118 weeks) in these 3 trials. Patients in these studies could elect to participate in an open-label extension study to examine the long-term safety of ESBRIET capsules (Study PIPF 012).
Table 2 below describes the related treatment-emergent adverse events occurring in ≥3% patients on ESBRIET capsules with a greater frequency than placebo in Studies PIPF-004, PIPF-006, and PIPF-016.
Table 2 Adverse Events Occurring in ≥3% Patients on ESBRIET Capsules and with Greater Frequency than Placebo in Studies PIPF-004, and PIPF-006, and PIPF-016
| Adverse Events | Number of Patients, n (%) | |
|---|---|---|
| Randomized Patient Subset Updated | ||
Pirfenidone (N = 623) | Placebo (N = 624) | |
| Gastrointestinal Disorders | ||
| Nausea | 225 (36.1) | 97 (15.5) |
| Abdominal paina | 165 (26.5) | 103 (16.5) |
| Diarrhoea | 161 (25.8) | 127 (20.4) |
| Dyspepsia | 115 (18.5) | 43 (6.9) |
| Vomiting | 83 (13.3) | 39 (6.3) |
| Gastro-oesophageal reflux disease | 69 (11.1) | 44 (7.1) |
| Dry mouth | 19 (3.0) | 17 (2.7) |
| General Disorders and Administration Site Conditions | ||
| Fatigue | 162 (26.0) | 119 (19.1) |
| Asthenia | 40 (6.4) | 24 (3.8) |
| Non-cardiac chest pain | 32 (5.1) | 25 (4.0) |
| Infections and Infestations | ||
| Upper respiratory tract infection | 167 (26.8) | 158 (25.3) |
| Sinusitis | 68 (10.9) | 64 (10.3) |
| Influenza | 41 (6.6) | 38 (6.1) |
| Gastroenteritis viral | 29 (4.7) | 17 (2.7) |
| Rhinitis | 20 (3.2) | 19 (3.0) |
| Injury, Poisoning And Procedural Complications | ||
| Sunburn | 23 (3.7) | 11 (1.8) |
| Investigations | ||
| Weight decreased | 63 (10.1) | 34 (5.4) |
| Gamma-Glutamyltransferase increased | 24 (3.9) | 11 (1.8) |
Adverse Events
| Number of Patients, n (%) | |||||
|---|---|---|---|---|---|
| Randomized Patient Subset Updated | |||||
Pirfenidone (N = 623) | Placebo (N = 624) | ||||
| Alanine Aminotransferase increased | 20 (3.2) | 9 (1.4) | |||
| Metabolism and Nutrition Disorders | |||||
| Decreased appetite | 129 (20.7.0) | 50 (8.0) | |||
| Musculoskeletal and Connective Tissue Disorders | |||||
| Arthralgia | 62 (10.0) | 44 (7.1) | |||
| Musculoskeletal Pain | 24 (3.9) | 22 (3.5) | |||
| Musculoskeletal Chest Pain | 19 (3.0) | 7 (1.1) | |||
| Nervous System Disorders | |||||
| Headache | 137 (22.0) | 120 (19.2) | |||
| Dizziness | 112 (18.0) | 71 (11.4) | |||
| Dysgeusia | 36 (5.8) | 14 (2.2) | |||
| Somnolence | 22 (3.5) | 18 (2.9) | |||
| Psychiatric Disorders | |||||
| Insomnia | 65 (10.4) | 41 (6.6) | |||
| Respiratory, Thoracic and Mediastinal Disorders | |||||
| Pharyngolaryngeal Pain | 38 (6.1) | 36 (5.8) | |||
| Epistaxis | 22 (3.5) | 21 (3.4) | |||
| Respiratory Tract Congestion | 21 (3.4) | 12 (1.9) | |||
| Skin and Subcutaneous Tissue Disorders | |||||
| Rash | 189 (30.3) | 64 (10.3) | |||
| Photosensitivity Reaction | 58 (9.3) | 7 (1.1) | |||
| Pruritus | 49 (7.9) | 33 (5.3) | |||
| Erythema | 25 (4.0) | 16 (2.6) | |||
| Dry Skin | 21 (3.4) | 11 (1.8) | |||
| Vascular Disorders | |||||
| Hot Flush | 25 (4.0) | 14 (2.2) | |||
| Hypertension | 20 (3.2) | 17 (2.7) | |||
a Includes abdominal pain, upper abdominal pain, abdominal distension, abdominal discomfort, and stomach discomfort.
Demographic Factors
No effect was seen between adverse events and sex (male versus female), age (<65 versus ≥65 years), or Baseline IPF severity (FVC <70% predicted versus FVC 70% to 80% predicted versus FVC ≥80% predicted) within the ESBRIET group. No effect also was seen for race (white versus non-white); however, there were only 65 non-white patients in the three predominantly North American Phase III studies combined.
Dose-Response Relationship (PIPF-004 and PIPF-006)
Study PIPF-004 included a group receiving a lower dose of ESBRIET (1197 mg/day) than the marketed dose of 2403 mg/day. Adverse drug reaction rates in the lower dose ESBRIET group were intermediate to the ESBRIET 2403 mg/day and placebo groups for a number of the more frequently occurring adverse drug reactions including nausea, dyspepsia, abdominal pain, decreased appetite, dizziness, headache, photosensitivity reaction and rash.
Adverse Drug Reactions in SP3
The safety analysis in the randomized, double-blind Phase III study (SP3) conducted in Japan included 109 patients who were treated with 1800 mg/day pirfenidone. This dose is comparable to the 2403 mg/day dose administered in studies PIPF-004 and PIPF-006 on a weight-normalized basis to account for the heavier body weight of the mostly North American patients in PIPF-004 and PIPF-006. In study SP3, 107 patients received placebo, and 55 patients received pirfenidone 1200 mg/day, for approximately 52 weeks. The adverse drug reaction profile for pirfenidone in the Japanese study, SP3, was generally similar to that observed with ESBRIET in studies PIPF-004 and PIPF-006 (primarily North American patients), with the exception of a higher incidence of photosensitivity reaction (51.4%) and a lower incidence of rash (9.2%) in patients on 1800 mg/day in the Japanese study. However, no photosensitivity reaction or rash was serious, severe, or life-threatening. The incidence of serious adverse drug reactions was 9.2% in the pirfenidone 1800 mg/day group and 5.6% in the placebo group.
Adverse Drug Reactions in Long-Term Studies
Study PIPF-012 was an uncontrolled, open-label extension, long-term, safety study which allowed patients who completed PIPF-004 and PIPF-006 to continue on pirfenidone treatment at 2403 mg/day or switch to pirfenidone 2403 mg/day from placebo treatment. A total of 603 patients were enrolled in Study PIPF-012. The mean duration of pirfenidone 2403 mg/day treatment in Study PIPF-012 was 27.5 weeks. The adverse drug reaction profile resulting from an interim analysis was similar to that observed in the Phase III trials and previous trials. No new safety signals or trends were observed.
8.2.1. Clinical Trial Adverse Reactions - Pediatrics
Not applicable.
8.3. Less Common Clinical Trial Adverse Reactions
Not applicable.
8.3.1. Less Common Clinical Trial Adverse Reactions - Pediatrics
Not applicable.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In studies PIPF 004 and PIPF 006, haematology and urinalysis parameters were similar between patients taking ESBRIET and placebo. Serum chemistry parameters were also similar across the groups with the exception of gamma glutamyl transferase (GGT) and creatinine. A mean increase at 72 weeks from Baseline in GGT level of 7.6 U/L was observed in the ESBRIET group while no change was seen in the placebo group. A mean decrease at 72 weeks from Baseline of 5.6 μmol/L in serum creatinine was observed in the ESBRIET group, compared with a mean decrease of 1.1 μmol/L in the placebo group. Few patients experienced shifts from Grade 0, 1, or 2 to Grade 3 or 4 in laboratory tests in the studies and across treatment groups. There was an imbalance between ESBRIET and placebo groups for shifts in hyponatraemia, hypophosphataemia and lymphopaenia, which were more frequent in the ESBRIET group.
Marked laboratory abnormalities in pooled data from studies PIPF-004, PIPF-006, and PIPF-016 occurred infrequently (≤1% per treatment group) and with no greater frequency in the ESBRIET group than in the placebo group, with the following exceptions in liver tests, lymphocytes, and hyponatremia. Patients treated with ESBRIET 2403 mg/day had a higher incidence of elevations in ALT or AST ≥3 × ULN than placebo patients (3.7% vs. 0.8%, respectively). Elevations ≥10 × ULN in ALT or AST occurred in 0.3% of patients in the ESBRIET 2403 mg/day group and in 0.2% of patients in the placebo group. Grade 0 to 3 reductions in lymphocyte count were seen in 6 ESBRIET patients (1.0%) and in 1 placebo patient (0.2%). One ESBRIET patient (0.2%) had a post-Baseline Grade 4 lymphocyte abnormality at Week 4, which was resolved at Week 6, Grade 2 at Weeks 12, 24, and 36, and resolved thereafter. Lymphocyte abnormalities were not associated with AEs. Grade 0 to 3 sodium (hyponatremia) abnormalities were reported in 9 ESBRIET patients (1.5%) and 1 placebo patient (0.2%).
8.5. Post-Market Adverse Reactions
Because post-marketing reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
In post-marketing experience in Japan many of the adverse events reported during post-approval use of pirfenidone (marketed as Pirespa) are consistent with the clinical trial experience with ESBRIET. These events include: abdominal discomfort, constipation, diarrhoea, dyspepsia, nausea, vomiting, ALT increased, AST increased, GGT increased, decreased appetite, dizziness, dysgeusia, somnolence, photosensitivity reaction, pruritus, rash.
The serious and unexpected adverse events include, but are not limited to, the following:
Blood and Lymphatic Disorders: Agranulocytosis, febrile neutropaenia, anaemia
Cardiac Disorders: Atrial fibrillation, palpitations, angina pectoris, ventricular tachycardia
Gastrointestinal Disorders: Gastric ulcer haemorrhage, gastritis, ileus
Metabolism and Nutrition Disorders: Dehydration, hyperkalaemia
General Disorders and Administration Site Condition: Pyrexia
Hepatobiliary Disorders: Bilirubin increased in combination with increases of ALT and AST, hepatic function abnormal, liver disorder, clinically relevant Drug-Induced Liver Injury ( uncommon) including isolated reports with fatal outcome
Immune System: Angioedema
Infections and Infestations: Bronchopulmonary aspergillosis, pneumonia, pneumonia bacterial, urinary tract infection
Investigations: C-reactive protein increased, hepatic enzyme increased, platelet count decreased, blood urea increased, renal impairment
Respiratory, Thoracic and Mediastinal Disorders: Lung disorder, pneumonitis, pneumothorax
Skin and Subcutaneous Tissue Disorders: Severe Cutaneous Adverse Reactions (SCARs) including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS)
9 DRUG INTERACTIONS
9.1. Serious Drug Interactions
Drug-Interactions with Inhibitors of CYP1A2 and Other CYP Isoenzymes Fluvoxamine ESBRIET is contraindicated in patients with concomitant use of fluvoxamine (a strong inhibitor of CYP1A2 with inhibitory effects on CYP2C9, 2C19, and 2D6). Fluvoxamine should be discontinued prior to the initiation of treatment with ESBRIET and avoided during ESBRIET therapy due to the potential for reduced clearance of pirfenidone (see 2 CONTRAINDICATIONS). Ciprofloxacin Co-administration of ESBRIET and 750 mg of ciprofloxacin (a moderate and selective inhibitor of CYP1A2) increased the exposure to pirfenidone by 81%. If ciprofloxacin at the dose of 750 mg twice daily (a total daily dose of 1500 mg) cannot be avoided, the dose of ESBRIET should be reduced to 1602 mg daily (a dose of 534 mg, three times a day). ESBRIET should be used with caution when ciprofloxacin is used at a total daily dose of 250 to 1000 mg (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION). Strong and Selective Inhibitors of CYP1A2 In vitro-in vivo extrapolations indicate that strong and selective inhibitors of CYP1A2 have the potential to increase the exposure to pirfenidone by approximately 2 to 4-fold. If concomitant use of ESBRIET with a strong and selective inhibitor of CYP1A2 cannot be avoided, the dose of ESBRIET should be reduced to 801 mg daily (267 mg, three times a day). Patients should be closely monitored for emergence of adverse reactions associated with ESBRIET therapy. Discontinue ESBRIET if necessary (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION). Other CYP1A2 Inhibitors Agents or combinations of agents that are moderate to strong inhibitors of both CYP1A2 and one or more other CYP isoenzymes involved in the metabolism of pirfenidone (i.e., CYP2C9, 2C19, 2D6, and 2E1) should be avoided during ESBRIET treatment. ESBRIET should be used with caution in patients treated with moderate inhibitors of CYP1A2 that do not inhibit other CYP isoenzymes. |
|---|
9.2. Drug Interactions Overview
Pirfenidone is primarily metabolized via CYP1A2 with minor contributions from other CYP isoenzymes including CYP2C9, 2C19, 2D6, and 2E1.
Patients should discontinue and avoid use of strong inhibitors of CYP1A2 due to the potential for reduced clearance of pirfenidone (see Table 3).
Patients should discontinue and avoid use of strong inducers of CYP1A2 to avoid reduced exposure to pirfenidone (see Table 3).
9.3. Drug-Behavioural Interactions
Cigarette Smoking and Inducers of CYP1A2: Cigarette smoking induces hepatic enzyme production, including CYP1A2, and thus may increase clearance of ESBRIET leading to reduced exposure. Patients should stop smoking before, and not smoke during ESBRIET therapy to avoid reduced exposure to pirfenidone. In a Phase I study the exposure to pirfenidone in smokers was significantly less than in non-smokers. Cigarette smoking should be avoided during ESBRIET therapy to prevent reduced exposure to pirfenidone.
9.4. Drug-Drug Interactions
In a Phase I study, the co-administration of ESBRIET and fluvoxamine (a strong inhibitor of CYP1A2 with inhibitory effects on other CYP isoenzymes [CYP2C9, 2C19, and 2D6]) resulted in an approximately 4-fold increase in exposure to pirfenidone in non-smokers.
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e. those identified as contraindicated)
Table 3 Established or Potential Drug-Drug Interactions
| Ref. | Effect | Clinical Comment | ||||||
|---|---|---|---|---|---|---|---|---|
| CYP1A2 Inhibitors | ||||||||
CYP1A2, 2C9, 2C19, 2D6: Fluvoxamine | CT | ↑4× AUC0-∞, ↑2× Cmax Increased exposure (and reduced clearance) | Concomitant therapy is contraindicated (see 7 WARNINGS AND PRECAUTIONS). | |||||
CYP1A2: Ciprofloxacin | CT | ↑81% AUC0-∞, ↑23% Cmax Increased exposure (and reduced clearance) | Concomitant therapy should be used with caution. Dose reductions may be needed (see 7 WARNINGS AND PRECAUTIONSand 4 DOSAGE AND ADMINISTRATION). | |||||
CYP1A2: Methoxsalen Mexiletine Oral contraceptives | T | ↑AUC0-∞, ↑Cmax Potential for increased exposure (and reduced clearance) | Concomitant therapy should be used with caution. | |||||
| Inhibitors of Other CYPs when Administered with CYP1A2 Inhibitors | ||||||||
| Ref. | Effect | Clinical Comment | |||||
|---|---|---|---|---|---|---|---|
CYP2C9: Amiodarone Miconazole | T | ↑AUC0-∞, ↑Cmax Potential for increased exposure (and reduced clearance) | Concomitant therapy with these agents and moderate-strong CYP1A2 inhibitors (listed above) should be discontinued and avoided. | ||||
CYP2C19: Fluconazole Esomeprazole Moclobemide Omeprazole Voriconazole | T | ↑AUC0-∞, ↑Cmax Potential for increased exposure (and reduced clearance) | Concomitant therapy with these agents and moderate-strong CYP1A2 inhibitors (listed above) should be discontinued and avoided. | ||||
CYP2D6: Bupropion Fluoxetine Paroxetine Quinidine Cinacalcet Duloxetine Terbinafine | T | ↑AUC0-∞, ↑Cmax Potential for increased exposure (and reduced clearance) | Concomitant therapy with these agents and moderate-strong CYP1A2 inhibitors (listed above) should be discontinued and avoided. | ||||
| CYP Inducers | |||||||
CYP1A2: Phenytoin | T | ↓AUC0-∞, ↓Cmax Potential for reduced exposure | Concomitant therapy should be discontinued and avoided. | ||||
CYP2C9: Carbamazepine Rifampin | T | ↓AUC0-∞, ↓Cmax Potential for reduced exposure | Concomitant therapy should be discontinued and avoided. | ||||
CYP2C9, 2C19: Rifampin | T | ↓AUC0-∞, ↓Cmax Potential for reduced exposure | Concomitant therapy should be discontinued and avoided. | ||||
| Legend: CT = Clinical Trial; T = Theoretical | |||||||
9.5. Drug-Food Interactions
Administration of ESBRIET capsules with food results in a large reduction in Cmax (by approximately 50%) and a smaller reduction in AUC, compared to the fasted state. Following oral administration of a single dose of 801 mg to healthy older adult volunteers (50–66 years of age) in the fed state, the rate of pirfenidone absorption slowed, while the AUC in the fed state was approximately 80 to 85% of the AUC observed in the fasted state. Less nausea and dizziness were observed in fed when compared with fasted subjects.
Therefore, ESBRIET should be administered with food to reduce the incidence of dizziness or nausea (see 4 DOSAGE AND ADMINISTRATION: Dosing Considerations).
A comparative bioavailability study was done to compare the new tablet formulation to the original capsule formulation. The effect of food on pirfenidone exposure was consistent between the tablet and capsule formulations (see 14 CLINICAL TRIALS).
Consumption of grapefruit juice is associated with inhibition of CYP1A2 and should be avoided during treatment with ESBRIET to prevent increased exposure to ESBRIET.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1. Mechanism of Action
The mechanisms of action of pirfenidone have not been fully established. However, existing data suggest that pirfenidone exerts anti-fibrotic and anti-inflammatory properties in a variety of in vitro systems and animal models of pulmonary fibrosis (e.g., bleomycin- and transplant-induced fibrosis).
IPF is a chronic fibrotic and inflammatory pulmonary disease affected by the synthesis and release of pro-inflammatory cytokines including tumour necrosis factor-alpha (TNF-α) and interleukin-1-beta (IL-1β). Pirfenidone attenuates fibroblast proliferation, production of fibrosis-associated proteins and cytokines, and the increased biosynthesis and accumulation of extracellular matrix in response to cytokine growth factors such as transforming growth factor-beta (TGF-β) and platelet-derived growth factor (PDGF). Pirfenidone has been shown to reduce the accumulation of inflammatory cells in response to various stimuli.
10.2. Pharmacodynamics
An observed dose-response relationship favouring a dose of 2403 mg/day pirfenidone compared with 1197 mg/day pirfenidone was observed in a Phase III randomized, double-blind, placebo-controlled study (PIPF-004). A PK-PD evaluation of a subset of these patients showed a weak positive relationship between pirfenidone plasma exposure and the primary endpoint of FVC change.
A double-blind, randomized, placebo- and active-controlled parallel arm study was performed to determine the impact of two doses of pirfenidone capsules (2403 mg/day & 4005 mg/day) on QT interval in healthy human volunteers (40/treatment arm). ECG assessments were performed at baseline and on day 10 of treatment. There was no evidence of a treatment-related effect on the QTc interval at either of the tested doses. Statistically significant increases in heart rate were observed, with maximum increases of 3.8 bpm (90% CI 1.7, 5.9) in the pirfenidone 2403 mg/day group and 4.9 bpm (90% CI 2.5, 7.4) in the pirfenidone 4005 mg/day group.
10.3. Pharmacokinetics
Table 4 Arithmetic Mean (Range) Pirfenidone Pharmacokinetic Parameters in Patients with IPF
| N | Cmax (µg/mL) | AUCa (mg•h/L) | Tmax (h) | ||
|---|---|---|---|---|---|
| IPF patients (PIPF-004) | 57 | 14.7 (6.48–33.6) | 180 (85.6–544) | not measured |
a: AUC0-24 estimates reflect three doses of 801 mg administered over the 24 hour period at steady-state
Absorption:
The absolute bioavailability of pirfenidone has not been determined in humans.
Administration of pirfenidone capsules with food results in a large reduction in Cmax (by around 50%) and a smaller reduction of AUC, compared to the fasted state. Following oral administration of a single dose of 801 mg to healthy older adult volunteers (50 to 66 years of age) in the fed state, the rate of pirfenidone absorption slowed, while the AUC in the fed state was approximately 80 to 85% of the AUC observed in the fasted state.
A comparative bioavailability study was done to compare the new tablet formulation to the original capsule formulation. Bioequivalence was demonstrated in both, the fasting and fed states when comparing the 801 mg tablet to three 267 mg capsules. The effect of food on pirfenidone exposure was consistent between the tablet and capsule formulations (see 14 CLINICAL TRIALS).
Following oral administration of a single dose of 801 mg of pirfenidone either as 3 x 267 mg capsules or 1 x 801 mg tablet in healthy adult volunteers, reduced incidences of adverse events (in particular nausea and dizziness) were observed in fed subjects when compared to the fasted group in a controlled setting (studies PIPF-005 and GP29830). Therefore, ESBRIET should be administered with food to reduce the incidence of dizziness or nausea (see 4 DOSAGE AND ADMINISTRATION: Dosing Considerations).
Distribution:
Pirfenidone binds to human plasma proteins, primarily to albumin. The overall mean binding ranged from 50% to 58% at concentrations observed in clinical studies (1 to 100 μg/mL). Mean apparent oral steady-state volume of distribution is approximately 70 L, indicating that pirfenidone distribution to tissues is modest.
Metabolism:
Pirfenidone is primarily metabolized via CYP1A2 (approximately 70–80%) with minor contributions from other CYP isoenzymes including CYP2C9, 2C19, 2D6, and 2E1. In vitro and in vivo studies to date have not detected any activity of the major metabolite, 5-carboxy-pirfenidone.
The clearance of oral pirfenidone appears modestly saturable. In a multiple-dose, dose-ranging study in healthy older adults administered doses ranging from 267 mg to 1335 mg three times a day, the mean clearance decreased by approximately 25% above a dose of 801 mg three times a day. The concentration-dependence of pirfenidone clearance did not appear to translate into a lack of dose proportionality in the Phase III trial and is not likely to be clinically relevant.
Pirfenidone was converted to 5-hydroxymethyl-pirfenidone and 5-carboxy-pirfenidone by NADPH-fortified human liver microsomes. The result of experiments with human recombinant CYP enzymes implicated several CYP enzymes such as CYP1A2, 2C9, 2C19, 2D6, and 2E1 in the metabolism of pirfenidone. However, the results of the antibody inhibition experiments and correlation analysis suggest that CYP1A2 is the major CYP enzyme responsible for the conversion of pirfenidone to 5-hydroxymethyl-pirfenidone and 5-carboxy-pirfenidone in human liver microsomes. The overall results indicate CYP1A2 as the major CYP involved in the metabolism, however, results from experiments with human recombinant CYP enzymes and correlation analysis indicate that other CYP enzymes participate in the overall metabolism of pirfenidone.
Pirfenidone was found not to significantly inhibit CYP or MAO enzymes. However under one experimental condition examined using human liver microsomes, pirfenidone caused direct inhibition of CYP1A2, CYP2A6, CYP2D6 and CYP2E1, as approximately 34%, 27%, 21% and 27% inhibition was observed at 1000 μM. As well, CYP enzymes are not influenced by 5-carboxy-pirfenidone and only mildly influenced by pirfenidone (at 250 μM).
Elimination
Following single dose administration of pirfenidone in healthy older adults, the mean apparent terminal elimination half-life was approximately 2.4 hours. Approximately 80% of an orally administered dose of pirfenidone is cleared in the urine within 24 hours of dosing. The majority of pirfenidone is excreted as the 5-carboxy-pirfenidone metabolite (>95% of that recovered), with less than 1% of pirfenidone excreted unchanged in urine.
Special Populations and Conditions
Population pharmacokinetic analyses were conducted, using data collected from four studies in healthy subjects or patients with renal impairment and one study in patients with IPF. Results showed no clinically relevant effects of age, gender or body size on the pharmacokinetics of pirfenidone.
- Pediatrics: The safety and effectiveness of ESBRIET in pediatric patients have not been established.
- Geriatrics: The independent effect of patient age on the PK of pirfenidone is relatively small (the predicted AUC for pirfenidone was approximately 23% higher in 80 year old compared to 50 year old patients) and unlikely to be clinically significant.
- Gender: No clinically relevant effect of gender on the pharmacokinetics of pirfenidone has been observed. The Cmax of pirfenidone in females was approximately 10% higher than in males.
- Race: No clinically relevant effect of race on the pharmacokinetics of pirfenidone has been observed. The predicted AUC0-24 of pirfenidone was found to be 21% lower in Caucasian compared with African-American subjects. However, there were only a small number of non-Caucasian patients included in controlled clinical trials.
- Body Size: No clinically relevant effect of body size on the pharmacokinetics of pirfenidone has been observed. Obese subjects were observed to have higher exposure than either normal or overweight subjects but the former were older and had worse renal function.
- Hepatic Insufficiency: The pharmacokinetics of pirfenidone were compared in subjects with moderate hepatic impairment (Child-Pugh Class B) and normal hepatic function. Results showed that there was a mean increase of 60% in pirfenidone exposure after a single dose of 801 mg pirfenidone (3 × 267 mg capsule) in patients with moderate hepatic impairment. Pirfenidone should be used with caution in patients with mild to moderate hepatic impairment and patients should be monitored closely for signs of toxicity especially if they are concomitantly taking a known CYP enzyme inhibitor (in particular a CYP1A2 inhibitor). ESBRIET is contraindicated in severe hepatic impairment and end stage liver disease (see 2 CONTRAINDICATIONS).
Renal Insufficiency: No significant differences in the pharmacokinetics of pirfenidone were observed in subjects with mild renal impairment (CrCl of 51–80 mL/min; Cockcroft-Gault equation) to severe renal impairment (CrCl <30 mL/min) compared with subjects with normal renal function (CrCl >80 mL/min). However, the parent drug is predominantly metabolized to 5-carboxy-pirfenidone, and the pharmacokinetics of this metabolite are altered in subjects with moderate to severe renal impairment. The AUC0-∞ of 5-carboxy-pirfenidone was significantly higher in the moderate (p = 0.009) and severe (p < 0.0001) renal impairment groups than in the group with normal renal function; 100 (26.3) and 168 (67.4) mg•h/L compared to 28.7 (4.99) mg•h/L
- respectively. However, the predicted amount of metabolite accumulation at steady state is minimal as the terminal elimination half-life is only 1–2 hours in these subjects. Caution is required in patients with mild to moderate renal impairment who are receiving pirfenidone. ESBRIET is contraindicated in patients with severe renal impairment (CrCl <30mL/min) or end stage renal disease requiring dialysis (see 7 WARNINGS AND PRECAUTIONS and 2 CONTRAINDICATIONS).
- Japanese Patients: Study SP3: a phase III study conducted in Japanese patients, compared pirfenidone 1800 mg/day (tablets, a comparable dose to 2403 mg/day in the North American and European populations of PIPF-004/006 on a weight-normalized basis) with placebo (N = 110, N = 109, respectively). Treatment with pirfenidone 1800 mg/day statistically significantly reduced mean decline in vital capacity (VC) at Week 52 (the primary endpoint) compared with placebo (-0.09 ± 0.02 L versus -0.16 ± 0.02 L respectively, relative difference 43.8%, p = 0.042). There was also a statistically significant prolongation in progression free survival compared with placebo (HR: 0.64 [0.43–0.96], p = 0.028).
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15 - 30°C).
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed via wastewater and disposal through household waste should be avoided. Use established “collection systems,” if available in your location.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions for ESBRIET.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | pirfenidone |
|---|---|
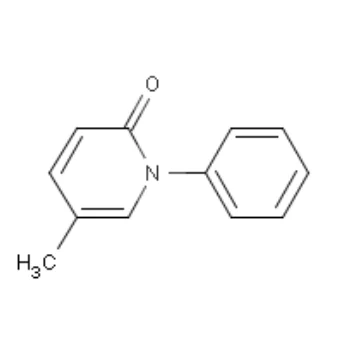
| Chemical name: | 5-Methyl-1-phenyl-2-(1H)-pyridone |
| Molecular formula and molecular mass : | C12H11NO and 185.22 |
| Structural formula: | |
| Physicochemical properties: | |
| Description: | White to pale yellow crystalline powder |
| Solubility: | Freely soluble in methanol, ethyl alcohol, acetone, and chloroform. Sparingly soluble in 1.0 N hydrochloric acid, water and 1.0 N sodium hydroxide. |
| Melting point: | Between 106°C and 112°C |
| pKa | 0.2 ± 0.6 |
14 CLINICAL TRIALS
14.1. Clinical Trials by Indication
Idiopathic Pulmonary Fibrosis
The clinical efficacy of ESBRIET (pirfenidone capsules 267 mg) has been studied in three Phase III, multicentre, randomized, double-blind, placebo-controlled studies in patients with IPF (PIPF-004, PIPF-006 and PIPF-016).
PIPF-004 and PIPF-006 compared treatment with ESBRIET 2403 mg/day to placebo. The studies were nearly identical in design, with few exceptions including an intermediate dose group (1197 mg/day) in PIPF-004. In both studies, treatment was administered three times daily for a minimum of 72 weeks. The final follow-up visit was held 3 to 4 weeks after the treatment completion visit. The primary
 |
endpoint in both studies was the change from Baseline to Week 72 in percent predicted Forced Vital Capacity (FVC).
PIPF-016 compared treatment with ESBRIET 2403 mg/day to placebo. Treatment was administered three times daily for 52 weeks. The primary endpoint was the change from Baseline to Week 52 in percent predicted FVC.
Table 5 Summary of Patient Demographics for Phase III Clinical Trials in Patients with IPF
| Study # | Trial design | Dosage, route of administration and duration | Study patients (n) Esbriet/ Control | Mean age (Range) | Gender | ||
|---|---|---|---|---|---|---|---|
| Esbriet | Control | Esbriet | Control | ||||
| PIPF-004 | Randomized double-blind, placebo-controlled Phase III study to evaluate the efficacy and safety of ESBRIET in patients with IPF | 2403 mg/day (three 267 mg capsules TID) ESBRIET vs. placebo, administered orally for 72 weeks. | 174/174 | 65.7 years (45–80 years) | 66.3 years (40–79 years) | 32.2% female | 26.4% female |
| PIPF-006 | Randomized double-blind, placebo-controlled Phase III study to evaluate the efficacy and safety of ESBRIET in patients with IPF | 2403 mg/day (three 267 mg capsules TID) ESBRIET vs. placebo, administered orally for 72 weeks. | 171/173 | 66.8 years (45–80 years) | 67.0 years (42–80 years) | 28.1% female | 28.3% female |
| PIPF-016 | Randomized double-blind, placebo-controlled Phase III study to evaluate the efficacy and safety of ESBRIET in patients with IPF | 2403 mg/day (three 267 mg capsules TID) ESBRIET vs. placebo, administered orally for 52 weeks. | 278/277 | 68.4 years (47–80 years) | 67.8 years (41–80 years) | 20.1% female | 23.1% female |
Forced Vital Capacity
In study PIPF-004, the decline in lung function, as measured by percent predicted FVC from Baseline at
Week 72 of treatment, was significantly reduced in patients receiving ESBRIET (N = 174) compared with patients receiving placebo (N = 174; p = 0.001, rank ANCOVA). The absolute difference in the mean change in percent predicted FVC was 4.4% between treatment groups, representing a relative difference of 35.5%. Treatment with ESBRIET also significantly reduced the decline of percent predicted FVC from Baseline at Weeks 24 (p = 0.014), 36 (p < 0.001), 48 (p < 0.001), and 60 (p < 0.001). At Week 72, a decline from Baseline in percent predicted FVC of ≥10% (a threshold indicative of the risk of mortality in IPF) was seen in 20% of patients receiving ESBRIET compared to 35% receiving placebo (Table 6).
In study PIPF-006, there was no statistically significant difference between treatment with ESBRIET (N = 171) and placebo (N = 173) in the reduction of the decline of percent predicted FVC from Baseline at Week 72 (p = 0.501, rank ANCOVA). However, treatment with ESBRIET reduced the decline in lung function, as measured by percent predicted FVC from Baseline at Weeks 24 (p < 0.001), 36 (p = 0.011), and 48 (p = 0.005). At Week 72, a decline in FVC of ≥10% was seen in 23% of patients receiving ESBRIET and 27% receiving placebo (Table 6).
The primary endpoint analysis of the pooled population also showed an ESBRIET treatment effect on percent predicted FVC at week 72 (p = 0.005, rank ANCOVA). The absolute difference in the mean change in percent predicted FVC was 2.5% between two treatment groups, representing a relative difference of 22.8%. At Week 72, a decline from Baseline in percent predicted FVC of ≥10% was seen in 21.4% of patients receiving ESBRIET compared to 30.5% receiving placebo (Table 6).
Table 6 Categorical Assessment of Change from Baseline to Week 72 in Percent Predicted FVC
| Number (% of Patients) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PIPF-004 | PIPF-006 | Pooled | ||||||||||
| ESBRIET 2403 mg/d (n = 174) | Placebo (n = 174) | ESBRIET 2403 mg/d (n = 171) | Placebo (n = 173) | ESBRIET 2403 mg/d (n = 345) | Placebo (n = 347) | |||||||
| Decline of ≥10% or death or lung transplant | 35 (20%) | 60 (34%) | 39 (23%) | 46 (27%) | 74 (21%) | 106 (30%) | ||||||
| Decline of <10% but ≥0% | 97 (56%) | 90 (52%) | 88 (52%) | 89 (51%) | 185 (54%) | 179 (52%) | ||||||
| Improvement of >0% | 42 (24%) | 24 (14%) | 44 (26%) | 38 (22%) | 86 (25%) | 62 (18%) | ||||||
In study PIPF 016, the decline of percent predicted FVC from Baseline at Week 52 of treatment, was significantly reduced in patients receiving ESBRIET (N = 278) compared with patients receiving placebo (N = 277; p < 0.000001, rank ANCOVA). Treatment with ESBRIET also significantly reduced the decline of percent predicted FVC from Baseline at Weeks 13 (p < 0.000001), 26 (p < 0.000001), and 39 (p = 0.00002).
Progression Free Survival (PFS)
In the analysis of PFS in study PIPF-004, treatment with ESBRIET significantly reduced the combined risk of death or disease progression by 36% compared to placebo (HR 0.64 [0.44–0.95]; p = 0.023). Disease progression was defined as ≥10% decline in percent predicted FVC or ≥15% decline in percent predicted diffusing capacity of the lungs for carbon monoxide (DLCO).
The reduction in risk was primarily due to differences in disease progression due to decline in percent predicted FVC. In study PIPF-006, there was no difference in PFS between the two treatment arms (HR 0.84 [0.58–1.22]; p = 0.355). In the pooled analysis, treatment with ESBRIET 2403 mg/day resulted in a 26% reduction in the risk of death or progression of disease compared with placebo (HR 0.74 [95% CI, 0.57–0.96]; p = 0.025).
In the analysis of PFS in study PIPF-016, treatment with ESBRIET significantly reduced the combined risk of death or disease progression by 43% compared to placebo (HR 0.57 [0.43–0.77]; p = 0.0001). Disease progression was defined as death, ≥10% decline in percent predicted FVC or ≥ 50 meters decline in six minute walk test (6MWT) distance.
Six Minute Walk Test Distance
In study PIPF-004, there was no difference between patients receiving ESBRIET compared to placebo in change from baseline to Week 72 of distance walked during a six minute walk test (6MWT) by the prespecified rank ANCOVA (p = 0.171). The difference in the mean decline in the 6MWT distance between the treatment groups at Week 72 was 16.4 meters, representing a relative difference of 21.3%.
In study PIPF-006, the decline in 6MWT distance from baseline to Week 72 was significantly reduced compared with placebo in this study (p < 0.001, rank ANCOVA). The difference in the mean decline in the 6MWT distance between the treatment groups at Week 72 was 31.8 meters, representing a relative difference of 41.3%.
In study PIPF-016, the decline in 6MWT distance from baseline to Week 52 was significantly reduced compared with placebo (p = 0.036, rank ANCOVA). The difference in the mean decline in the 6MWT distance between the treatment groups was 26.7 meters, representing a relative difference of 44.2%.
Mortality
The overall survival was captured as an exploratory efficacy endpoint in pivotal studies. The cause of death was not adjudicated and the effect of ESBRIET on all-cause mortality is inconclusive.
In a pooled analysis of survival in PIPF-004 and PIPF 006 the mortality rate with ESBRIET 2403 mg/day group was 7.8% compared with 9.8% with placebo (HR 0.77 [95% CI, 0.47–1.28]).
In Study PIPF-016, the mortality rate with ESBRIET 2403 mg/ day group was 4.0 % compared with 7.2% with placebo (HR 0.55 [ 95% CI, 0.26–1.15]).
14.2. Comparative Bioavailability Studies
Study GP29830 was a Phase I, open-label, randomized, four-treatment period, four-sequence, single dose, crossover comparative bioavailability study designed to determine the bioequivalence of pirfenidone tablets (1 x 801 mg) to pirfenidone capsules (3 x 267 mg) under both fasted and fed conditions in 44 healthy male (64%) and female (36%) subjects from 20 to 54 years of age. The results from 43 subjects are presented below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILAIBLITY DATA
Fasting Conditions
PIRFENIDONE (1 x 801 mg for Tablet; 3 x 267 mg for Capsules) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Tablet* | Capsules† | % Ratio of Geometric Least Square Means | 90% Confidence Interval |
AUCT (ng • hr/mL) | 49200 52200 (35.4) | 49500 52300 (34.1) | 99.63 | 96.66-102.69 |
AUCI (ng • hr/mL) | 49400 52400 (35.9) | 49700 52600 (34.5) | 99.61 | 96.64-102.68 |
Cmax (ng/mL) | 12600 13400 (39.6) | 12500 13000 (34.5) | 101.26 | 94.41-108.60 |
Tmax§ (h) | 1.00 (0.25, 3.00) | 0.75 (0.25, 2.00) | -- | -- |
T½2 (h) | 2.77 (20.6) | 2.77 (21.3) | -- | -- |
*Test product, ESBRIET (pirfenidone) 801 mg tablets (Hoffmann-La Roche Limited), n=42
† Reference product, ESBRIET (pirfenidone) 267 mg capsules, manufacturer: F.Hoffmann-La Roche, country of purchase: USA, n=42
AUCT = area under the plasma concentration versus time curve from time zero to the time of the last quantifiable concentration up to 24 hours post dosing
AUCI = area under the plasma concentration versus time curve from time zero to infinity
§ Expressed as the median (range)
2 Expressed as the arithmetic mean (CV%)
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILAIBLITY DATA
Fed Conditions (High Fat Meal)
PIRFENIDONE (1 x 801 mg for Tablet; 3 x 267 mg for Capsules) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Tablet* | Capsules† | % Ratio of Geometric Least Square Means | 90% Confidence Interval |
AUCT (ng • hr/mL) | 40600 43100 (35.8) | 39500 42000 (36.6) | 103.06 | 99.55-106.69 |
AUCI (ng • hr/mL) | 40900 43400 (36.5) | 39800 42400 (37.3) | 103.05 | 99.54-106.69 |
Cmax (ng/mL) | 7640 7910 (26.0) | 6560 6760 (24.8) | 116.61 | 108.26-125.60 |
Tmax§ (h) | 2.05 (1.00, 6.00) | 3.00 (0.50, 6.00) | -- | -- |
T½2 (h) | 2.74 (21.1) | 2.75 (21.3) | -- | -- |
*Test product, ESBRIET (pirfenidone) 801 mg tablets (Hoffmann-La Roche Limited), n=43
† Reference product, ESBRIET (pirfenidone) 267 mg capsules, manufacturer: F.Hoffmann-La Roche, country of purchase: USA, n=43
AUCT = area under the plasma concentration versus time curve from time zero to the time of the last quantifiable concentration up to 24 hours post dosing
AUCI = area under the plasma concentration versus time curve from time zero to infinity
§ Expressed as the median (range)
2 Expressed as the arithmetic mean (CV %)
14.3. Immunogenicity
Not applicable.
15 MICROBIOLOGY
No microbiological information is required for this product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
With the exception of phototoxicity, nonclinical data revealed no special hazard for humans based on conventional studies of safety pharmacology, repeated dose toxicity, genotoxicity, carcinogenicity, and toxicity to reproduction. Phototoxicity and irritation were noted in guinea pigs and mice after oral administration of pirfenidone and with exposure to UVA light.
Acute Toxicity
In mice and rats the clinical signs observed at the maximum non-lethal doses included hypoactivity and abnormal gait. These clinical signs were observed in dogs in addition to vomiting, mydriasis and tremors. In a study with rats, the toxicity of pirfenidone was reduced when administered with food. Pirfenidone was more toxic to female rats and female dogs in which higher systemic exposures compared to males was observed.
Table 7 Acute Toxicity
| Species | Route | Maximum Non-Lethal Dose (mg/kg) | Minimum Lethal Dose (mg/kg) |
|---|---|---|---|
| Mouse | Oral, gavage | 1000 | 2000 |
| Rat | Oral, gavage | 500 (fasted); 1000 (fed) | 1000 (fasted) |
| Dog | Oral, capsule | 1000 | Not determined |
Chronic toxicity
In repeated dose studies, decreased body weight was observed in mice, rats and dogs administered oral pirfenidone. Increased liver weights were observed with hepatic centrilobular hypertrophy and increased CYP content in all species. In dogs, transient vomiting, abnormal gait, tremors, limb weakness, rigidity and hypoactivity were observed at doses 10-fold higher (Cmax) than the clinical dose. The toxic signs observed in these studies were reversible after pirfenidone administration was stopped.
Table 8 Chronic Toxicity
| Species | Route | Duration | Doses (mg/kg/day) | Results |
|---|---|---|---|---|
| Mouse, B6C3F1 | Oral, diet | 13 weeks | 0, 200, 600, 2000 | ↓ Body weight at the highest dose. ↑ Red blood cell indices, reticulocyte ratio and platelet count in males. ↓ Albumin (both sexes), A/G ratio (males), total protein (females) and cholesterol; ↑ BUN (males). Dose-related ↑ liver weight with centrilobular hepatocyte hypertrophy, and splenic extramedullary hematopoiesis in males at 2000 mg/kg/day. NOAEL: 600 mg/kg/day |
| Rat, F344 | Oral, diet | 13 weeks | 0, 500, 1000, 1500 | ↓ Body weight and body weight gain, ↓ erythrocytes (RBC), haemoglobin, and hematocrit and ↑ MCV, platelets and reticulocytes in both sexes. ↑Total protein, albumin, glucose, BUN, cholesterol, calcium, and inorganic phosphorous; ↓ A/G ratio, triglycerides and chloride. ↑ Liver, kidney, adrenal, and testes weights. Dose-dependent centrilobular hepatocyte hypertrophy, kidney tubular epithelial regeneration (males only), and adrenal gland zone fasciculata hypertrophy (males only at 1500 mg/kg/day). |
| Rat, SD | Oral, gavage | 6 months | 0, 20, 100, 500, 1000 | Salivation, ↓ activity, and respiratory rate at 500 and 1000 mg/kg/day during the first 6 weeks of treatment. ↓ Food consumption and body weight gain in high-dose males. ↓ RBC, haemoglobin, and hematocrit in females, and ↑ MCV and MCH in males, together with ↓ prothrombin time in males and ↑ activated partial thromboplastin time in females. ↑ Total protein, albumin, A/G ratio, creatinine kinase, amylase, |
| Species | Route | Duration | Doses (mg/kg/day) | Results | ||
|---|---|---|---|---|---|---|
cholesterol, calcium, and inorganic phosphorous; ↓ creatinine, triglycerides, and chloride. ↑ Liver weight (both sexes) and centrilobular hypertrophy in 2/12 males at 1000 mg/kg/day. ↑ CYP content and selected isoenzymes at 500 and 1000 mg/kg/day. NOAEL: 100 mg/kg/day | ||||||
| Rat, SD | Intravenous | 4 weeks | 0, 500, 1000, 1625 | Ten deaths by Day 4 of treatment (1 female at 1000 mg/kg/day and 9 females at 1625 mg/kg/day). ↑ Absolute liver and kidney weights and hepatic centrilobular hypertrophy at 1625 mg/kg/day. NOAEL: 500 mg/kg/day | ||
| Dog, Beagle | Oral, capsule | 3 months | 0, 20, 70, 200 | Mucous in faeces, salivation, vomiting, abnormal gait, difficulty in standing, rigidity, limb weakness, head shakes, vocalization and hypoactivity at the higher doses. ↑ Platelet counts at 200 mg/kg/day. ↑ Alkaline phosphatase at 70 and 200 mg/kg/day. ↑ Liver weight and reversible hepatocellular hypertrophy at 200 mg/kg/day. ↑ Submaxillary gland weight and acinar hypertrophy at 200 mg/kg/day. ↑ CYP content and microsomal enzyme activities at all doses. NOAEL: 70 mg/kg/day | ||
| Dog, Beagle | Oral, capsule | 9 months | 0, 20, 70, 200 | Mucous in faeces (all doses), salivation, vomiting, abnormal gait, difficulty standing, rigidity, limb weakness, head shakes, vocalization and hypoactivity at the higher doses. ↓ Body weight (females), ↑ platelet counts, ↑ alkaline phosphatase, ↑ liver weight with reversible hepatocellular hypertrophy, ↑ submaxillary gland weight and acinar hypertrophy at 200 mg/kg/day. ↑ CYP content and microsomal enzyme activities at all doses. NOAEL: 70 mg/kg/day | ||
| Dog, Beagle | Oral, capsule | 9 months | 0, 20, 70, 200 (given as b.i.d.) | Excessive salivation and reddening of the inner ear skin. And ↑ alkaline phosphatase at the higher doses. NOAEL: 200 mg/kg/day | ||
A/G = albumin/globulin; MCV = mean corpuscular volume; MCH = mean corpuscular haemoglobin; BUN = blood urea nitrogen; RBC = red blood cells; SD = Sprague Dawley; NOAEL = no observed adverse effect level.
Carcinogenicity:
In long term studies, an increased incidence of liver tumours (hepatocellular adenoma) was observed in mice (≥800 mg/kg/day) and rats (≥750 mg/kg/day). At a pirfenidone dose of 1500 mg/kg/day (4-fold higher than the clinical dose), a statistically significant increase in uterine adenocarcinoma was observed in female rats. The results of mechanistic studies indicated that the occurrence of uterine tumours may be related to a chronic dopamine-mediated sex hormone imbalance involving a species specific endocrine mechanism in the rat which is not present in humans. The relevance of these findings to humans is unknown.
Table 9 Carcinogenicity
| Species and Strain | Route | Duration | Doses (mg/kg/day) | Results |
|---|---|---|---|---|
| Mouse, B6C3F1 | Oral, diet | 104 weeks | 0, 800, 2000, 5000 | ↑ Liver tumours at all doses (both sexes): considered to be a rodent species-specific non-genotoxic effect due to hepatic CYP induction. |
| Rat, F344 | Oral, diet | 104 weeks | 0, 375, 750, 1500 | ↑ Liver tumours at all doses (both sexes): considered to be rodent species-specific non-genotoxic effect due to hepatic CYP induction. ↑ uterine tumours at 1500 mg/kg/day: considered to be rodent species-specific due to chronic dopamine-mediated sex hormone imbalance. |
Genotoxicity and Photogenotoxicity:
Pirfenidone showed no genotoxic potential in standard in vitro and in vivo genotoxicity assays. However, under UV exposure, pirfenidone was positive in a photoclastogenic assay in Chinese hamster lung cells but was not mutagenic in the Ames test. The metabolite 5-carboxy-pirfenidone was not photomutagenic or photoclastogenic in similar assays.
Table 10 Genotoxicity and Photogenotoxicity
| Type of Study | Test System | Method of admin. | Doses | Results |
|---|---|---|---|---|
| Ames | S. typhimurium, E. coli | In vitro | 100–5000 μg/plate | Negative |
| Chromosome Aberration | Chinese hamster ovary cells | In vitro | 1000–2800 μg/mL (no activation) 500–1400 μg/mL (with activation) | Negative |
| Chromosome Aberration | Chinese hamster lung cells | In vitro | 231–1850 μg/mL (with and without activation) 116–925 μg/mL (without activation, 48 hr exposure) | Negative |
| Bone marrow micronucleus | Mouse, ICR | Oral, gavage (single dose) | 200, 400, 800 mg/kg | Negative |
| Liver UDS | Rat, F344 | Oral, gavage (single dose) | 1000, 2000 mg/kg | Negative |
| Ames | S typhimurium strains TA102 and TA98, E coli strain WP2/pKM101 | In vitro | 39.1–5000 μg/plate (without activation, with UV exposure) | Negative |
| Chromosome Aberration | Chinese hamster lung cells | In vitro | 560–1900 μg/mL (without activation, in the absence of UV exposure) | Negative |
| Chromosome Aberration | Chinese hamster lung cells | In vitro | 1–120 μg/mL (without activation, with UV exposure) | Positive |
UDS = Unscheduled DNA synthesis
Reproductive and Developmental Toxicology:
Reproductive toxicology studies demonstrated no adverse effects of pirfenidone on male and female fertility or postnatal development of offspring in rats. Rats exhibited prolongation of the estrus cycle and an increased incidence of irregular cycles at higher doses (≥450 mg/kg/day). Prolonged gestation and reduced fetal viability were observed in rats at high doses (≥1000 mg/kg/day). The placental transfer of pirfenidone and/or its metabolites occurred in animals with the potential for their accumulation in amniotic fluid. Dose-related increases in fetal incidences of soft tissue variations and skeletal variations were observed but were considered related to lower maternal food consumption and body weight. There was no evidence of teratogenicity in rats or rabbits at doses up to 4-fold higher than the clinical dose. Pirfenidone and/or its metabolites were also excreted in milk in lactating rats.
Table 11 Reproductive Toxicity
| Species and Strain | Route | Duration | Doses (mg/kg/day) | Results |
|---|---|---|---|---|
| Rat, SD | Oral, diet | 50–69 days: Premating (28 days M and 14 days F) to Gestation Day 20 | 0, 450, 900 | ↓ Body weight and food consumption at both dose levels. ↓ Gravid uterine weights and foetal body weights. NOAEL (fertility and foetal development): 900 mg/kg/day. |
| Rat, SD | Oral, gavage | 50–69 days: Premating (28 days M and 14 days F) to Gestation Day 17 | 0, 50, 150, 450, 1000 | Transient hypoactivity, ptosis, limb weakness, abnormal gait, and hypopnea (both sexes) at 150, 450, and 1000 mg/kg/day. Dose-related prolongation of estrus cycle and high incidence of irregular cycles at 450 and 1000 mg/kg/day. NOAEL (reproductive toxicity, males): 1000 mg/kg/day NOAEL (reproductive toxicity, females): 150 mg/kg/day NOAEL (foetal development): 1000 mg/kg/day |
| Rabbit, Japanese white | Oral, gavage | Gestation Days 6 to 18 | 0, 30, 100, 300 | Transient accelerated respiration, prone position, dilation of auricular blood vessels, sluggish startle reaction, ear drop, scant feces, salivation, and ptosis at 100 and 300 mg/kg/day. ↓ Food consumption and ↓ body weight gain. One animal at 100 mg/kg/day delivered prematurely on Day 28 and two animals aborted (Day 24 and Day 26) and another died (Day 27) at 300 mg/kg/day. NOAEL (reproductive toxicity): 30 mg/kg/day NOAEL (foetal development): 300 mg/kg/day |
| Rat, SD | Oral, gavage | Gestation Day 7 to Lactation Day 20 (postpartum) | 0, 100, 300, 1000 | F0: ↓ activity, respiratory inhibition, salivation, and lacrimation at all doses. Prolongation of gestation period at 1000 mg/kg/day (22.7 days versus 22.2 days in control) and decreased foetal viability. F1: ↓ Body weights during pre-weaning period at 300 and 1000 mg/kg/day. F2: no effect on litter size. |
SD = Sprague Dawley; NOAEL = no observed adverse effect level.
Special Toxicology:
Phototoxicity
Pirfenidone was phototoxic in guinea pigs and mice inducing transient erythema at doses 4-fold higher than the clinical dose (based on Cmax). Sunscreens with SPF 50+ prevented pirfenidone induced phototoxicity in guinea pigs.
Table 12 Phototoxicity and Photosensitivity
| Species and Strain | Route | Duration | Doses (mg/kg/day) | Results |
|---|---|---|---|---|
| Guinea pig, Hartley | Oral, gavage / topical | 1 day/ 2 weeks | 0, 40, 160 (oral); 0%, 1%, 5% (topical) | No phototoxicity or photosensitivity |
| Guinea pig, Hartley | Oral, gavage | 3 days | 0, 2.5, 10, 40, 160 | Reversible phototoxic effects. |
| Guinea pig, Hartley | Oral, gavage | Single dose | 0, 160 | Severity of phototoxic lesions ↓ over time after UV exposure and was minimal at 6 hours post-dose. |
| Guinea pig, Hartley | Oral, gavage | Single dose | 0, 160 | Severity of phototoxic lesions ↓ with ↑ grade of sunscreen. SPF 50 cream and SPF 50 lotion decreased the total toxicity score by 100% and 74%, respectively. |
Mouse, HR-1 Hairless | Oral, gavage | 28 days | 0, 500 | Local toxicity of skin: mild acanthosis and mild single cell necrosis in the epidermis of the auricle and the dorsal skin. These changes were not apparent after a 1-month recovery period. |
UV = ultraviolet; SPF = sun protection factor
Juvenile Toxicity:
Not applicable.