


Product Monograph - Herzuma
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ..................................................................................................................... 4
1.1 Pediatrics .................................................................................................................... 5
1.2 Geriatrics .................................................................................................................... 5
2 CONTRAINDICATIONS ..................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .......................................................... 5
4 DOSAGE AND ADMINISTRATION .................................................................................... 6
4.1 Dosing Considerations ............................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment .......................................................... 6
4.3 Administration ............................................................................................................. 8
4.4 Reconstitution ............................................................................................................. 9
4.5 Missed Dose ............................................................................................................. 10
5 OVERDOSAGE ................................................................................................................ 11
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 11
7 DESCRIPTION .................................................................................................................. 12
8 WARNINGS AND PRECAUTIONS .................................................................................. 12
8.1 Special Populations .................................................................................................. 25
8.1.1 Pregnant Women ................................................................................................... 25
8.1.2 Breast-feeding ....................................................................................................... 26
8.1.3 Pediatrics ............................................................................................................... 26
8.1.4 Geriatrics (> 65 years of age) ................................................................................ 26
9 ADVERSE REACTIONS ................................................................................................... 27
9.1 Clinical Trial Adverse Drug Reactions ...................................................................... 27
9.2 Less Common Clinical Trial Adverse Reactions ...................................................... 61
9.3 Post-Market Adverse Drug Reactions ...................................................................... 65
10 DRUG INTERACTIONS .................................................................................................... 66
10.1 Overview .................................................................................................................. 66
10.2 Drug-Drug Interactions ............................................................................................. 67
11 ACTION AND CLINICAL PHARMACOLOGY .................................................................. 67
11.1 Mechanism of Action ................................................................................................ 67
11.2 Pharmacokinetics ..................................................................................................... 68
12 STORAGE, STABILITY AND DISPOSAL ........................................................................ 69
13 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 70
PART II: SCIENTIFIC INFORMATION ......................................................................................... 71
14 PHARMACEUTICAL INFORMATION .............................................................................. 71
15 COMPARATIVE CLINICAL TRIALS ................................................................................ 72
15.1 Comparative Trial Design and Study Demographics ............................................... 72
15.2 Comparative Study Results ...................................................................................... 73
15.2.1 Comparative Bioavailability Studies ....................................................................... 74
15.2.1.1 Pharmacokinetics .............................................................................................. 74
15.2.2 Comparative Safety and Efficacy ........................................................................... 74
15.2.2.1 Efficacy .............................................................................................................. 74
15.2.2.2 Safety ................................................................................................................ 75
15.2.2.3 Immunogenicity ................................................................................................. 75
16 COMPARATIVE NON-CLINICAL PHARMACOLOGY AND TOXICOLOGY ................... 75
16.1 Comparative Non-Clinical Pharmacodynamics ........................................................ 75
16.2 Comparative Toxicology ........................................................................................... 76
17 CLINICAL TRIALS – REFERENCE BIOLOGIC DRUG ................................................... 76
18 NON-CLINICAL TOXICOLOGY– REFERENCE BIOLOGIC DRUG ................................ 94
19 SUPPORTING PRODUCT MONOGRAPHS .................................................................. 103
PATIENT MEDICATION INFORMATION .................................................................................. 104
PATIENT MEDICATION INFORMATION .................................................................................. 111
HERZUMA® (trastuzumab) is a biosimilar biologic drug (biosimilar) to HERCEPTIN®.
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Indications have been granted on the basis of similarity between HERZUMA® and the reference biologic drug HERCEPTIN®.
Early Breast Cancer (EBC)
HERZUMA® (trastuzumab) is indicated for the treatment of patients with early stage breast cancer with ECOG 0-1 status, whose tumours overexpress HER2,
- following surgery and after chemotherapy
- following adjuvant chemotherapy consisting of doxorubicin and cyclophosphamide, in combination with paclitaxel or docetaxel
- in combination with adjuvant chemotherapy consisting of docetaxel and carboplatin.
For detailed information on the inclusion criteria for the clinical trials of trastuzumab in EBC according to the TNM (Tumour, Node, Metastasis) classification system, see Part II: Clinical Trial – Reference Biologic Drug section.
Based on the analysis of the HERA trial, the benefit of the adjuvant treatment with trastuzumab for low risk patients not given adjuvant chemotherapy are unknown.
The comparative efficacy and safety between different chemotherapy regimens (i.e. concurrent versus sequential, anthracycline containing versus non-anthracycline containing) was not studied.
Metastatic Breast Cancer (MBC)
HERZUMA® is indicated for the treatment of patients with MBC whose tumours overexpress HER2.
The benefits of treatment with trastuzumab in patients who do not overexpress HER2 (HER2 expression 0 as defined by a validated immunohistochemical [IHC] assay) or who exhibit lower-level expression (HER2 expression 1+ as defined by a validated IHC assay, and the subgroup of patients with HER2 overexpression 2+ as defined by a validated IHC assay that corresponds to 1+ scoring by the investigative clinical trial assay), are unclear (see WARNINGS AND PRECAUTIONS: Selection of Patients / Diagnostic Tests).
HERZUMA® can be used in combination with pertuzumab and docetaxel for the treatment of patients with HER2-positive metastatic breast cancer who have not received prior anti-HER2 therapy or chemotherapy for metastatic disease. For information on the use of HERZUMA® in combination with pertuzumab and docetaxel, consult the Product Monograph for pertuzumab.
Metastatic Gastric Cancer (MGC)
HERZUMA® in combination with capecitabine or intravenous 5-fluorouracil and cisplatin is indicated for the treatment of patients with HER2 positive metastatic adenocarcinoma of the stomach or gastro-esophageal junction who have not received prior anti-cancer treatment for their metastatic disease.
HERZUMA® should only be administered to patients with MGC whose tumours have HER2 overexpression as defined by IHC 2+ confirmed by FISH+, or IHC 3+ as determined by an accurate and validated assay.
1.1 Pediatrics
The safety and effectiveness of HERZUMA® in pediatric patients (< 18 years of age) have not been established.
1.2 Geriatrics
The reported clinical experience is not adequate to determine whether older patients respond differently to trastuzumab treatment than younger patients (see WARNINGS AND PRECAUTIONS, Geriatrics).
2 CONTRAINDICATIONS
- HERZUMA® (trastuzumab) is contraindicated in patients with known hypersensitivity to trastuzumab, Chinese Hamster Ovary (CHO) cell proteins, or any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- When using in combination with pertuzumab and docetaxel, consult Product Monographs for pertuzumab and docetaxel for further information on these drugs.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
There is a risk of medication errors between HERZUMA® (trastuzumab) and KADCYLA® (trastuzumab emtansine). In order to minimize this risk, check the vial labels to ensure that the drug being prepared and administered is HERZUMA® (trastuzumab) and not KADCYLA® (trastuzumab emtansine). HERZUMA® should be prescribed using both the trade name and non-proprietary name (see DOSAGE AND ADMINISTRATION, Dosing Considerations). Cardiotoxicity HERZUMA® (trastuzumab) can result in the development of ventricular dysfunction and congestive heart failure. In the adjuvant treatment setting, the incidence of cardiac dysfunction was higher in patients who received trastuzumab plus chemotherapy versus chemotherapy alone. An increase in the incidence of symptomatic and asymptomatic cardiac events was observed when trastuzumab was administered after anthracycline-containing chemotherapy compared to administration with a non-anthracycline regimen of docetaxel and carboplatin. The incidence was more marked when trastuzumab was |
|---|
administered concurrently with a taxane than when administered sequentially to a taxane. In the metastatic setting, the incidence and severity of cardiac dysfunction was particularly high in patients who received trastuzumab concurrently with anthracyclines and cyclophosphamide (see WARNINGS AND PRECAUTIONS, Cardiovascular). Evaluate left ventricular function in all patients prior to and during treatment with HERZUMA® (see WARNINGS AND PRECAUTIONS, Cardiovascular). Infusion Reactions; Pulmonary Toxicity HERZUMA® administration can result in serious infusion reactions and pulmonary toxicity. Fatal infusion reactions have been reported. In most cases, symptoms occurred during or within 24 hours of administration of trastuzumab. HERZUMA® infusion should be interrupted for patients experiencing dyspnea or clinically significant hypotension. Patients should be monitored until signs and symptoms completely resolve. Discontinue HERZUMA® for infusion reactions manifesting as anaphylaxis, angioedema, interstitial pneumonitis, or acute respiratory distress syndrome (see WARNINGS AND PRECAUTIONS). Embryo-Fetal Toxicity Exposure to HERZUMA® during pregnancy can result in impairment of fetal renal growth and/or renal function impairment resulting in oligohydramnios and oligohydramnios sequence manifesting as pulmonary hypoplasia, skeletal abnormalities, intrauterine growth retardation and neonatal death (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
There is a risk of medication errors between HERZUMA® (trastuzumab) and KADCYLA® (trastuzumab emtansine). In order to prevent medication errors, it is important to check the vial labels to ensure that the drug being prepared and administered is HERZUMA® (trastuzumab) and not KADCYLA® (trastuzumab emtansine). Ensure that the recommended HERZUMA® (trastuzumab) dose is administered (see Recommended Dose and Dosage Adjustment section).
HERZUMA® should be prescribed using both the trade name and non-proprietary name. Do not substitute HERZUMA® for or with KADCYLA® (trastuzumab emtansine).
When using in combination with pertuzumab and docetaxel for treatment of patients with HER-2-positive metastatic breast cancer, consult Product Monographs for pertuzumab and docetaxel for further information, such as dose adjustment, sequence of administration of each medication and duration of treatment.
4.2 Recommended Dose and Dosage Adjustment
Early Breast Cancer (EBC)
3-Weekly Schedule: The recommended initial loading dose is 8 mg/kg HERZUMA® (trastuzumab) administered as a 90-minute infusion. The recommended maintenance dose is 6 mg/kg HERZUMA® 3 weeks later and then 6 mg/kg repeated at 3-weekly intervals administered as infusions over approximately 90 minutes. If the prior dose was well tolerated, the dose can be administered as a 30-minute infusion. Do not administer as an IV push or bolus (see Preparation for Administration).
Weekly schedule: As a weekly regimen, the recommended initial loading dose of HERZUMA® is 4 mg/kg followed by 2 mg/kg every week.
See clinical trial – reference biological drug section for chemotherapy combination dosing.
Metastatic Breast Cancer (MBC)
Weekly schedule: The recommended initial loading dose is 4 mg/kg HERZUMA® administered as a 90-minute infusion. The recommended weekly maintenance dose is 2 mg/kg HERZUMA® and can be administered as a 30-minute infusion if the initial loading dose was well tolerated. HERZUMA® may be administered in an outpatient setting. Do not administer as an IV push or bolus (see Preparation for Administration).
Metastatic Gastric Cancer (MGC)
3-Weekly Schedule: The recommended initial loading dose is 8 mg/kg HERZUMA® administered as a 90-minute infusion. The recommended maintenance dose is 6 mg/kg HERZUMA® 3 weeks later and then 6 mg/kg repeated at 3-weekly intervals administered as infusions over approximately 90 minutes. If the prior dose was well tolerated, the dose can be administered as a 30-minute infusion. Do not administer as an IV push or bolus (see Preparation for Administration)
Duration of Treatment
In clinical studies, patients with MBC or MGC were treated with trastuzumab until progression of disease. Patients with EBC should be treated for 1 year or until disease recurrence or unacceptable cardiac toxicity, whichever occurs first (see WARNINGS AND PRECAUTIONS, Cardiovascular). Extending treatment in EBC beyond one year is not recommended (see Clinical Trials – Reference Biological Drug, Early Breast Cancer (EBC), HERA).
Dose Reduction
No reductions in the dose of trastuzumab were made during clinical trials. Patients may continue therapy with HERZUMA® during periods of reversible, chemotherapy-induced myelosuppression, but they should be monitored carefully for complications of neutropenia during this time. The specific instructions to reduce or hold the dose of chemotherapy should be followed.
Table 1 depicts the criteria for permanent discontinuation of trastuzumab for cardiac dysfunction in pivotal studies in adjuvant breast cancer.
Table 1 Criteria for Permanent Discontinuation for Cardiac Dysfunction in Pivotal Studies in Adjuvant Breast Cancer
| STUDY | If Symptomatic CHF | If Held for Asymptomatic LVEF Decrease (per algorithm used in each study protocol) |
|---|---|---|
| HERA | required | required if trastuzumab held for 2 consecutive cycles |
| NSABP B-31, NCCTG N9831 and BCIRG-006 | required | required if trastuzumab held for 2 consecutive cycles, or for 3 intermittent cycles; investigator may choose to discontinue permanently sooner |
Dose Holding
Monitoring of Cardiac Function (also see WARNINGS AND PRECAUTIONS, Cardiovascular, Cardiotoxicity)
Table 2 Recommendations for Continuation or Withdrawal of HERZUMA® Therapy in Asymptomatic Patients Based on Serial Measurements of Left Ventricular Ejection Fraction (LVEF)a
(Adapted from the Canadian Consensus Guidelines*)
| Relationship of LVEF to LLN | Asymptomatic decrease in LVEF from baseline | |||
|---|---|---|---|---|
| ≤ 10 percentage points | 10–15 percentage points | ≥ 15 percentage points | ||
| Within radiology facility’s normal limits | Continue HERZUMA® | Continue HERZUMA® | Hold HERZUMA® and repeat MUGA or ECHO after 4 weeks | |
| 1–5 percentage points below LLN | Continue HERZUMA® b | Hold HERZUMA® and repeat MUGA or ECHO after 4 weeks b,c | Hold HERZUMA® and repeat MUGA or ECHO after 4 weeks c,d | |
| ≥6 percentage points below LLN | Continue HERZUMA® and repeat MUGA or ECHO after 4 weeksd | Hold HERZUMA® and repeat MUGA or ECHO after 4 weeks c,d | Hold HERZUMA® and repeat MUGA or ECHO after 4 weeks c,c | |
a Based on NSABP B-31 trial protocol. Modified to include recommendations for cardiology consultation or treatment of cardiac dysfunction (or both) when appropriate, as indicated in the subsequent footnotes. b Consider cardiac assessment and initiation of angiotensin converting-enzyme inhibitor therapy. c After two holds, consider permanent discontinuation of HERZUMA®. d Initiate angiotensin converting-enzyme inhibitor therapy and refer to cardiologist. LLN = lower limit of normal; MUGA = multiple-gated acquisition scan; ECHO = echocardiography. *Source: Mackey JR, Clemons M, Côté MA, et al. Cardiac management during adjuvant trastuzumab therapy: recommendations of the Canadian Trastuzumab Working Group. Curr Oncol. 2008 Jan;15(1):24-35. | ||||
For the frequency of cardiac monitoring see WARNINGS AND PRECAUTIONS, Cardiovascular, Cardiotoxicity.
Health Canada has not authorized an indication for pediatric use (see Indications section).
4.3 Administration
Weekly Schedule: Treatment may be administered in an outpatient setting by administration of a 4 mg/kg loading dose of HERZUMA® by intravenous (IV) infusion over 90 minutes. Do not administer as an IV push or bolus. Patients should be observed for fever and chills or other infusion associated symptoms. Serious adverse reactions to infusions of trastuzumab including dyspnea, hypotension, hypertension, wheezing, bronchospasm, tachycardia, reduced oxygen saturation and respiratory distress have been reported infrequently (also see ADVERSE REACTIONS). Interruption of the infusion may help control such symptoms. The infusion may be resumed when symptoms abate.
If prior infusion was well tolerated, subsequent weekly doses of 2 mg/kg HERZUMA® may be administered over 30 minutes (see Recommended Dose and Dosage Adjustment). Patients should still be observed for fever and chills or other infusion-associated symptoms (see ADVERSE REACTIONS).
3-Weekly Schedule: Treatment may be administered in an outpatient setting by administration of an 8 mg/kg loading dose of HERZUMA® by intravenous (IV) infusion over 90 minutes. Do not administer as an IV push or bolus. Patients should be observed for fever and chills or other infusion associated symptoms (see ADVERSE REACTIONS). Interruption of the infusion may help control such symptoms. The infusion may be resumed when symptoms abate.
If prior infusion was well tolerated, subsequent 3-weekly doses of 6 mg/kg HERZUMA® may be administered over 30 minutes (see Recommended Dose and Dosage Adjustment). Patients should still be observed for fever and chills or other infusion-associated symptoms (see ADVERSE REACTIONS).
HERZUMA® should not be mixed or diluted with other drugs. Infusions of HERZUMA® should not be administered or mixed with dextrose solutions.
Flush the intravenous line with 0.9% Sodium Chloride Injection, USP after each dose.
4.4 Reconstitution
Table 3 Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
| 440 mg/vial | 20 mL of Bacteriostatic Water for Injection (BWFI) | 21 mL | 21 mg/mL trastuzumab |
| 150 mg/vial | 7.2 mL of Sterile Water for Injection (SWFI) | 7.4 mL | 21 mg/mL trastuzumab |
Preparation for Administration
Use appropriate aseptic technique.
440 mg/vial
Each vial of HERZUMA® should be reconstituted with 20 mL of BWFI, containing 1.1% benzyl alcohol, as supplied, to yield a multi-dose solution containing 21 mg/mL trastuzumab. Immediately upon reconstitution with BWFI, the vial of HERZUMA® must be labelled with “Do not use after:” followed by the future date that is 28 days from the date of reconstitution.
If the patient has a known hypersensitivity to benzyl alcohol, HERZUMA® must be reconstituted with Sterile Water for Injection (see WARNINGS AND PRECAUTIONS). HERZUMA® which has been reconstituted with SWFI must be used immediately and any unused portion discarded. Use of other reconstitution diluents should be avoided.
150 mg/vial
Each vial of HERZUMA® should be reconstituted with 7.2 mL of Sterile Water for Injection (SWFI) (not supplied), to yield a single-dose solution containing 21 mg/mL trastuzumab. The reconstituted solution should be used immediately and any remaining reconstituted solution should be discarded.
HERZUMA® should be carefully handled during reconstitution. Causing excessive foaming during reconstitution or shaking the reconstituted HERZUMA® may result in problems with the amount of HERZUMA® that can be withdrawn from the vial.
Reconstitution:
440 mg/vial
- 1. Using a sterile syringe, slowly inject 20 mL of Bacteriostatic Water for Injection in the vial containing the lyophilized HERZUMA® directing the stream into the lyophilized cake.
- 2. Swirl vial gently to aid reconstitution. Do not shake.
150 mg/vial
- 1. Using a sterile syringe, slowly inject 7.2 mL of Sterile Water for Injection (not supplied) in the vial containing the lyophilized HERZUMA® directing the stream into the lyophilized cake.
- 2. Swirl vial gently to aid reconstitution. Do not shake.
Slight foaming of the product upon reconstitution is not unusual. Allow the vial to stand undisturbed for approximately 5 minutes. The reconstituted HERZUMA® results in a colorless to pale yellow transparent solution and should be essentially free of visible particles.
Determine the volume in mL of HERZUMA® solution needed:
Weekly Schedule: based on a loading dose of 4 mg trastuzumab/kg body weight or a maintenance dose of 2 mg trastuzumab/kg body weight. Volume (mL)= [Body Weight (kg) x Dose (4 mg/kg for loading OR 2 mg/kg for maintenance)] 21 mg/mL (concentration of reconstituted solution)
3-Weekly Schedule: based on a loading dose of 8 mg trastuzumab/kg body weight, or a subsequent 3 weekly dose of 6 mg trastuzumab/kg body weight:
Volume (mL)= [Body Weight (kg) x Dose (8 mg/kg for loading OR 6 mg/kg for maintenance)] 21 mg/mL (concentration of reconstituted solution)
Withdraw the appropriate volume of solution calculated from the vial and add it to an infusion bag containing 250 mL of 0.9% sodium chloride, USP. Dextrose (5%) solution should not be used since it causes aggregation of the protein. To mix the solution and avoid foaming, invert the bag gently. The reconstituted preparation results in a colourless to pale yellow transparent solution. Parenteral drug products should be inspected visually for particulates and discolouration prior to administration. No incompatibilities between HERZUMA® and polyvinylchloride, polyethylene or polypropylene bags have been observed.
4.5 Missed Dose
Weekly schedule: If the patient has missed a dose of HERZUMA® by one week or less, then the usual maintenance dose (2 mg/kg) should be given as soon as possible (do not wait until the next planned cycle). Subsequent maintenance HERZUMA® doses of 2 mg/kg should be administered 7 days later according to the weekly schedule.
If the patient has missed a dose of HERZUMA® by more than one week, a re-loading dose of HERZUMA® should be administered (4 mg/kg over approximately 90 minutes) as soon as possible. Subsequent maintenance HERZUMA® doses of 2 mg/kg should be administered 7 days later according to the weekly schedule.
3-Weekly Schedule: If the patient has missed a dose of HERZUMA® by one week or less, then the usual maintenance dose (6 mg/kg) should be administered as soon as possible (do not wait until the next planned cycle). Subsequent maintenance HERZUMA® doses of 6 mg/kg should be administered 21 days later according to the 3-weekly schedule.
If the patient has missed a dose of HERZUMA® by more than one week, a re-loading dose of HERZUMA® should be administered (8 mg/kg over approximately 90 minutes) as soon as possible. Subsequent maintenance HERZUMA® doses of 6 mg/kg should be administered 21 days later according to the 3-weekly schedule.
5 OVERDOSAGE
There is no experience with overdosage in human clinical trials. Single doses higher than 500 mg (10 mg/kg) have not been tested.
Ensure that the recommended HERZUMA® (trastuzumab) dose and NOT KADCYLA® (trastuzumab emtansine) dose is administered. For information on the risk of KADCYLA® overdose due to medication errors, see KADCYLA® Product Monograph. For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 4 Dosage Forms, Strengths, Composition and Packaging
Composition:
HERZUMA® (trastuzumab) is a sterile, white to pale yellow, preservative-free lyophilized powder for intravenous (IV) administration.
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| IV Infusion | Lyophilized powder for reconstitution 440 mg tratruzumab/vial 150 mg trastuzumab/vial | L-histidine, L-histidine HCl, polysorbate 20, α,α-trehalose dihydrate. Note: The Bacteriostatic Water for Injection (BWFI) supplied with HERZUMA® (trastuzumab) 440 mg/vial contains 1.1% benzyl alcohol (see WARNINGS AND PRECAUTIONS). The Sterile Water for Injection (SWFI) for dilution of the 150 mg/vial is not supplied. |
440 mg/vial
Each vial of HERZUMA® contains 440 mg trastuzumab, 6.4 mg L-histidine, 9.9 mg L-histidine HCl, 1.8 mg polysorbate 20, and 879 mg α,α-trehalose dihydrate. Reconstitution with 20 mL of the supplied BWFI, containing 1.1% benzyl alcohol as a preservative, yields a multi-dose solution containing 21 mg/mL trastuzumab, at a pH of approximately 6.
150 mg/vial
Each vial of HERZUMA® contains 150 mg trastuzumab, 2.2 mg L-histidine, 3.4 mg L-histidine HCl, 0.6 mg polysorbate 20, and 299.6 α,α-trehalose dihydrate. Reconstitution with 7.2 mL of the SWFI (not supplied), yields a single-dose solution containing 21 mg/mL trastuzumab, at a pH of approximately 6.
Availability:
440 mg/vial
HERZUMA® is supplied as a lyophilized, sterile powder containing 440 mg trastuzumab per vial under vacuum.
BWFI is supplied as a 20 mL vial of sterile solution containing 1.1% benzyl alcohol as an antimicrobial preservative.
Each carton contains one vial of 440 mg HERZUMA® and one 20 mL vial of BWFI containing 1.1% benzyl alcohol.
150 mg/vial
HERZUMA® is supplied as a lyophilized, sterile powder containing 150 mg trastuzumab per vial under vacuum.
Each carton contains one vial of 150 mg HERZUMA®.
7 DESCRIPTION
- HERZUMA® (trastuzumab) is a biosimilar to HERCEPTIN®. It consists of humanized immunoglobulin G1 (IgG1) monoclonal antibody that selectively binds with high affinity to extra cellular domain (ECD) of the human epidermal growth factor receptor 2 (HER2).
8 WARNINGS AND PRECAUTIONS
Please see the Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information.
General
Therapy with HERZUMA® should only be initiated under supervision of a physician experienced in the treatment of cancer patients.
When using in combination with pertuzumab and docetaxel, consult Product Monographs for pertuzumab and docetaxel for further information on these drugs.
In order to improve traceability of biological medicinal products, the trade name and the batch number of the administered product should be clearly recorded (or stated) in the patient file.
Early Breast Cancer (EBC)
The safety of the various combination chemotherapy regimens prior to trastuzumab therapy was not separately analyzed in the HERA trial. The data provided in the Product Monograph reflects the safety and efficacy of trastuzumab for the recommended 1 year treatment duration.
Benzyl Alcohol: Benzyl alcohol, used as a preservative in BWFI, has been associated with toxicity in neonates and children up to 3 years old. For patients with a known hypersensitivity to benzyl alcohol (the preservative in BWFI), reconstitute HERZUMA® with Sterile Water for Injection (SWFI). Use SWFI-reconstituted HERZUMA® immediately and discard the vial (see DOSAGE AND ADMINISTRATION).
Cardiovascular
Cardiotoxicity: Administration of HERZUMA® can result in the development of ventricular dysfunction and congestive heart failure. In the adjuvant treatment setting, the incidence of cardiac dysfunction was higher in patients who received trastuzumab plus chemotherapy versus chemotherapy alone. In patients with EBC, an increase in the incidence of symptomatic and asymptomatic cardiac events was observed when trastuzumab was administered after anthracycline-containing chemotherapy compared to administration with a non-anthracycline regimen of docetaxel and carboplatin. The incidence was more marked when trastuzumab was administered concurrently with a taxane than when administered sequentially to a taxane. In the metastatic setting, the incidence and severity of cardiac dysfunction were particularly high in patients who received trastuzumab concurrently with anthracyclines and cyclophosphamide. The incidence of cardiac adverse events was also higher in patients with previous exposure to anthracyclines based on post-market data.
Because the half-life of trastuzumab, using a population pharmacokinetic method, is approximately 28.5 days (95% CI, 25.5 - 32.8 days), trastuzumab may persist in the circulation for approximately 24 weeks (range: 22-28 weeks) after stopping treatment with HERZUMA®. Since the use of an anthracycline during this period could possibly be associated with an increased risk of cardiac dysfunction, a thorough assessment of the risks versus the potential benefits is recommended in addition to careful cardiac monitoring. If possible, physicians should avoid anthracycline based therapy while trastuzumab persists in the circulation.
Patients who receive HERZUMA® either as a component of adjuvant treatment or as a treatment for metastatic HER2 positive breast cancer may experience signs and symptoms of cardiac dysfunction such as dyspnea, increased cough, paroxysmal nocturnal dyspnea, peripheral edema, S3 gallop, or reduced ejection fraction. Cardiac dysfunction associated with therapy with HERZUMA® may be severe and has been associated with disabling cardiac failure, death, and mural thrombosis leading to stroke.
Left ventricular function should be evaluated in all patients prior to and during treatment with HERZUMA®. If LVEF drops 10 ejection points from baseline and/or to below 50%, HERZUMA® should be withheld and a repeat LVEF assessment performed within approximately 3 weeks. If LVEF has not improved, or declined further, discontinuation of HERZUMA® should be strongly considered, unless the benefits for the individual patient are deemed to outweigh the risks. The scientific basis of cardiac dysfunction has been incompletely investigated in pre-clinical studies.
Extreme caution should be exercised in treating patients with pre-existing cardiac dysfunction, and in EBC, in those patients with an LVEF of 55% or less. Candidates for treatment with HERZUMA® as part of adjuvant treatment for operable breast cancer or for MBC, especially those with prior anthracycline and cyclophosphamide (AC) exposure, should undergo thorough baseline cardiac assessment including history and physical exam, electrocardiogram (ECG) and either 2D echocardiogram or multiple gated acquisition (MUGA) scan. A careful risk-benefit assessment should be made before deciding to treat with HERZUMA®. Cardiac assessments, as performed at baseline, should be repeated every 3 months during treatment and every 6 months following discontinuation of treatment until 24 months from the last administration of HERZUMA®. In patients with EBC who receive anthracycline containing chemotherapy further monitoring is recommended, and should occur yearly up to 5 years from the last administration of HERZUMA®, or longer if a continued decrease of LVEF is observed. Monitoring may help to identify patients who develop cardiac dysfunction. Patients who develop asymptomatic cardiac dysfunction may benefit from more frequent monitoring (e.g. every 6-8 weeks). If patients have a continued decrease in left ventricular function, but remain asymptomatic, the physician should consider discontinuing therapy unless the benefits for the individual patient are deemed to outweigh the risks.
If symptomatic cardiac failure develops during therapy with HERZUMA®, it should be treated with the standard medications for this purpose. Discontinuation of HERZUMA® should be strongly considered in patients who develop clinically significant congestive heart failure. In the MBC clinical trials, approximately two-thirds of patients with cardiac dysfunction were treated for cardiac symptoms, most patients responded to appropriate medical therapy (which may include one or more of the following: diuretics, angiotensin-converting enzyme inhibitors, β-blockers, angiotensin II receptor blockers, or cardiac glycosides) often including discontinuation of trastuzumab. The safety of continuation or resumption of trastuzumab in patients who have previously experienced cardiac toxicity has not been prospectively studied.
Early Breast Cancer (EBC)
HERZUMA® and anthracyclines should not be given concurrently in the adjuvant treatment setting.
Risk factors for a cardiac event identified in four large adjuvant studies included advanced age (> 50 years), low level of baseline and declining LVEF (< 55%), low LVEF prior to or following the initiation of paclitaxel treatment, trastuzumab treatment, and prior or concurrent use of anti-hypertensive medications. In patients receiving trastuzumab after completion of adjuvant chemotherapy the risk of cardiac dysfunction was associated with a higher cumulative dose of anthracycline given prior to initiation of trastuzumab and a high body mass index (BMI > 25 kg/m2).
In EBC, the following patients were excluded from the HERA, JA (NSABP B-31 and NCCTG N9831) and BCIRG-006 trials there are no data about the benefit risk balance, and therefore treatment cannot be recommended in such patients:
- history of myocardial infarction (MI),
- angina pectoris requiring medication,
- history of or present CHF (NYHA II–IV),
- other cardiomyopathy,
- cardiac arrhythmia requiring medication,
- clinically significant cardiac valvular disease,
- poorly controlled hypertension (hypertension controlled by standard medication eligible) and
- clinically significant pericardial effusion.
The safety of continuation or resumption of trastuzumab in patients who have previously experienced cardiac toxicity has not been prospectively studied. According to the narrative reports of cardiac events, about half of the events had resolved completely by the time of the interim analysis. Please see
Table 7 and
Table 8 below.
For patients with EBC, cardiac assessments, as performed at baseline, should be repeated every 3 months during treatment and every 6 months following discontinuation of treatment until 24 months from the last administration of HERZUMA®. In patients who receive anthracycline containing chemotherapy further monitoring is recommended, and should occur yearly up to 5 years from the last administration of HERZUMA®, or longer if a continued decrease of LVEF is observed.
A high index of clinical suspicion is warranted for discontinuing treatment in the setting of cardiopulmonary symptoms. Close monitoring of cardiac function should be carried out for all patients and adequate treatment for CHF should be administered regardless of the discontinuation of HERZUMA® therapy. Please see Table 2 in DOSAGE AND ADMINISTRATION: Dose Holding, Monitoring of Cardiac Function, for information on continuation and discontinuation of HERZUMA® based on interval LVEF assessments.
HERA
In the HERA trial, cardiac monitoring (electrocardiogram [ECG], left ventricular ejection fraction [LVEF], signs/symptoms and cardiac questionnaire) was performed at baseline and regularly throughout the study. The assessment schedule for cardiac monitoring was at months 3 and 6 and then every 6 months until month 36 (3 years from the date of therapy) and in month 60 (5 years from the date of therapy). In addition, LVEF was measured at 48 months (4 years from the date of therapy) and followed up every 12 months from year 6 to year 10.
When trastuzumab was administered after completion of adjuvant chemotherapy, NYHA class III-IV heart failure was observed in 0.6% of patients in the one-year arm after a median follow-up of 12 months.
Table 5 Absolute Numbers and Rates of Cardiac Endpoints in HERA (Median follow-up of 12 months)
| HERA study | Observation | Trastuzumab |
|---|---|---|
| n (%) | n (%) | |
| N=1708 | N=1678 | |
| Primary cardiac endpoint | 1 (0.1%) | 10 (0.6%) |
| Secondary cardiac endpoint | 9 (0.5%) | 51 (3.0%) |
| Total “cardiac endpoints” | 10 (0.6%) | 61 (3.6%) |
Table 6 Absolute Numbers and Rates of Cardiac Endpoints in HERA (Median follow-up of 8 years)
| HERA study | Observation | Trastuzumab |
|---|---|---|
| n (%) | 1 year arm | |
| N=1744 | n (%) | |
| N=1682 | ||
| Primary cardiac endpoint | 2 (0.1%) | 14 (0.8%) |
| Events after 1 year | 0 (0.0%) | 1 (0.1%) |
| Secondary cardiac endpoint | 15 (0.9%) | 78 (4.6%) |
| (69 – excluding patients with primary endpoint) | ||
| Events after 1 year | 7 (0.4%) | 14 (0.8%) |
| (13 – excluding patients with primary endpoint) | ||
| Total “cardiac endpoints” | 17 (1.0%) | 83 (4.9%) |
Table 7 Median Time to Return to Baseline LVEF/ Stabilizations of LVEF in the HERA Trial (Median follow-up of 8 years) - Primary Cardiac Endpoint
| HERA study | Primary Cardiac Endpoint | |||||
|---|---|---|---|---|---|---|
Observation (n = 2) | trastuzumab 1-year (n=14) | |||||
| Return to baseline LVEF | 0 | 11 (79%) | ||||
| Median time to return to baseline LVEF | - | 218 d | ||||
| Stabilization of LVEF | 0 | 5 (36%) | ||||
Table 8 Median Time to Return to Baseline LVEF/ Stabilizations of LVEF in the HERA Trial (Median follow-up of 8 years) - Secondary Cardiac Endpoint
| HERA study | Secondary Cardiac Endpoint (excluding patients with primary cardiac endpoint) | ||||||
|---|---|---|---|---|---|---|---|
Observation (n = 15) | trastuzumab 1-year (n=69) | ||||||
| Return to baseline LVEF | 10 (67%) | 60 (87%) | |||||
| Median time to return to baseline LVEF | 189 d | 240 d | |||||
| Stabilization of LVEF | 4 (27%) | 18 (26%) | |||||
A significant drop in left ventricular ejection fraction (LVEF) is defined as an absolute decrease of 10 EF points or more from baseline and to below 50%, measured by MUGA scan or echocardiogram.
A primary cardiac endpoint was defined as the occurrence at any time after randomization but prior to any new therapy for recurrent disease of symptomatic congestive heart failure of NYHA class III or IV, confirmed by a cardiologist and a significant drop in LVEF, or cardiac death.
A secondary cardiac endpoint was defined as asymptomatic (NYHA class I) or mildly symptomatic (NYHA class II) cardiac dysfunction with a significant LVEF drop. In addition events which did not meet the above criteria for a secondary cardiac endpoint but which in the opinion of the Cardiac Advisory Board should be classed as secondary cardiac endpoints were included.
After a median follow-up of 3.6 years the incidences of severe CHF, symptomatic CHF and at least one significant LVEF decrease (an absolute decline of at least 10% from baseline LVEF and to less than 50%) after 1 year of trastuzumab therapy was 0.8%, 1.9% and 9.8%, respectively.
After a median follow-up of 8 years the incidence of severe CHF (NYHA III & IV) in the trastuzumab 1 year treatment arm was 0.8%, and the rate of mild symptomatic and asymptomatic left ventricular dysfunction was 4.6%. At least one LVEF assessment was missing for 20.8% of patients in the observation only arm and 32.0% of patients in the trastuzumab 1-year arm. During the follow-up until month 60, at least one LVEF assessment was missed for 18.0% of patients in the observation only arm and 17.9% of patients in the trastuzumab 1-year arm.
Reversibility of severe CHF (defined as a sequence of at least two consecutive LVEF values ≥50% after the event) was evident for 71.4% of trastuzumab-treated patients. Reversibility of mild symptomatic and asymptomatic left ventricular dysfunction was demonstrated for 79.5% of patients. Approximately 17% (14/83) of cardiac endpoints occurred after completion of trastuzumab in the trastuzumab one-year arm.
Joint Analysis: NSABP B-31 and NCCTG N9831
Cardiac dysfunction adverse events were defined in both B-31 and N9831 as symptomatic cardiac events and asymptomatic LVEF events. Symptomatic cardiac events were reviewed and confirmed by the cardiac committee of each study and included the occurrence of symptomatic congestive heart failure with objective findings and confirmation by imaging, deaths due to cardiac causes (CHF, MI, or documented primary arrhythmia) and probable cardiac deaths (sudden death without documented etiology). Asymptomatic LVEF events were defined as absolute drop in LVEF ≥10% to < 55% or an absolute drop in LVEF of ≥5% to below the institution’s lower limit of normal (LLN). In study B-31, 15.5% of patients discontinued trastuzumab due to asymptomatic LVEF decrease (12.2%), CHF (2.2%) or Cardiac diagnosis other than CHF (1.1%) in the trastuzumab + chemotherapy arm; no patients in the chemotherapy alone arm discontinued treatment for these reasons. In all analyses the rate of cardiac dysfunction was higher in patients in the trastuzumab + chemotherapy arm compared with those in the chemotherapy alone arm. From the paclitaxel baseline to the six month, nine month and eighteen month assessment, the average change in LVEF was more pronounced in the trastuzumab + chemotherapy arm (-4.2%, -5.1% and -3.1% in the trastuzumab + chemotherapy alone arm, respectively versus -0.5%, -0.4% and -0.9% in the chemotherapy alone arm, respectively).
Table 9 Joint Analysis: (NSABP B-31 and NCCTG N9831)
The Incidence and Type of Cardiac Events (Median Duration of More Than 8 Years** Safety Follow up)
| B31 | N9831 | B-31+N9831 | |||||
|---|---|---|---|---|---|---|---|
| AC→T | AC→T + H | AC→T | AC→T + H | AC→T | AC→T + H | ||
| (n = 889) | (n = 1031) | (n = 766) | (n = 969) | (n = 1655) | (n = 2000) | ||
| Symptomatic CHF (non-death) | 11 (1.2%) | 38 (3.7%) | 5 (0.7%) | 24 (2.5%) | 16 (1.0%)a | 62 (3.1%)b | |
| Cardiac death | 2 (0.2%)c | 1 (0.1%) | 3 (0.4%) | 1 (0.1%) | 5 (0.3%)c | 2 (0.1%) | |
| Death due to CHF, MI, or primary arrhythmia | 0 (0.0%) | 0 (0.0%) | 2 (0.3%) | 1 (0.1%) | 2 (0.1%) | 1 (0.1%) | |
| Sudden death without documented etiology | 2 (0.2%) | 1 (0.1%) | 1 (0.1%) | 0 (0.0%) | 3 (0.2%) | 1 (0.1%) | |
| B31 | N9831 | B-31+N9831 | ||||
|---|---|---|---|---|---|---|
| AC→T | AC→T + H | AC→T | AC→T + H | AC→T | AC→T + H | |
| (n = 889) | (n = 1031) | (n = 766) | (n = 969) | (n = 1655) | (n = 2000) | |
| Any cardiac or asymptomatic LVEF events | 270 (30.4%) | 401 (38.9%) | 209 (27.3%) | 367 (37.9%) | 479 (28.9%) | 768 (38.4%) |
| Drop in LVEF of 10 points compared with baseline to below 55* | 236 (26.5%) | 376 (36.5%) | 184 (24.0%) | 340 (35.1%) | 420 (25.4%) | 716 (35.8%) |
| Drop in LVEF of 5 points compared with baseline to below the lower limit of normal* | 161 (18.1%) | 267 (25.9%) | 127 (16.6%) | 238 (24.6%) | 288 (17.4%) | 505 (25.3%) |
A = doxorubicin; C = cyclophosphamide; CHF = congestive heart failure; H = trastuzumab; LVEF = left ventricular ejection fraction; MI = myocardial infarction; T = paclitaxel. *Asymptomatic LVEF per protocol events at any time after AC initiation: 1. Drop in LVEF of 10 points compared with AC baseline LVEF to below 55. or 2. Drop in LVEF of 5 points compared with AC baseline LVEF to below the lower limit of normal. ** In the joint analysis safety population, the median duration of follow-up was 8.1 years for the AC→T + H group and 8.5 years for the AC→T group a 16 AC→T patients had adjudicated and confirmed symptomatic CHF out of the 62 possible CHF patients reviewed by the study committees. b 62 AC→T + H patients had adjudicated and confirmed symptomatic CHF out of the 135 possible CHF patients reviewed by the study committees. c A patient received AC→T in study B-31; not included here and had “emphysema” listed on autopsy. | ||||||
At 3 years, the cardiac event rate in patients receiving AC→TH (doxorubicin plus cyclophosphamide followed by paclitaxel + trastuzumab) was estimated at 3.2%, compared with 0.9% in AC→T treated patients. Between 5 and 7 years of follow-up, an additional patient in each treatment group experienced a cardiac event; the cardiac event rate at 9 years follow-up in patients receiving AC→TH was estimated at 3.2%, compared with 1.0% in AC→T treated patients.
Table 10 summarizes the follow-up information for 84 patients (52 from study B-31 and 32 from study N9831) for whom symptomatic CHF was adjudicated and confirmed by the study committee.
Table 10 Joint Analysis (NSABP B-31 and NCCTG N9831)
Follow-Up of Symptomatic CHF Events (Median Duration of More Than 8 Years* Safety Follow up)
(Patients from the Joint Safety Population with Symptomatic CHF Confirmed by Study Committee)
| B-31 | N9831 | Joint Analysis | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
AC→T (n = 11) | AC→T + H (n = 38) | AC→T (n = 5) | AC→T + H (n = 24) | AC→T (n = 16) | AC→T + H (n = 62) | |||||||||||||||
| Months from onset to first overall recovery | ||||||||||||||||||||
| N | 4 | 22 | 0 | 9 | 4 | 31 | ||||||||||||||
| Mean (SD) | 10.1 (2.2) | 21.5 (11.1) | NA | 10.5 (8.6) | 10.1 (2.2) | 18.3 (11.5) | ||||||||||||||
| Median | 10.2 | 16.9 | NA | 6.6 | 10.2 | 14.5 | ||||||||||||||
| Range | 8–12 | 9–50 | NA | 3–31 | 8–12 | 3–50 | ||||||||||||||
| B-31 | N9831 | Joint Analysis | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
AC→T (n = 11) | AC→T + H (n = 38) | AC→T (n = 5) | AC→T + H (n = 24) | AC→T (n = 16) | AC→T + H (n = 62) | |||||
| Current overall recovery status | ||||||||||
| Recovery (LVEF ≥ 50% and no symptoms) | 3 (27.3%) | 8 (21.1%) | (0.0%) | 7 (29.2%) | 3 (18.8%) | 15 (24.2%) | ||||
| No recovery (LVEF < 50% or symptoms) | 2 (18.2%) | 7 (18.4%) | 3 (60.0%) | 6 (25.0%) | 5 (31.3%) | 13 (21.0%) | ||||
| Unknown | 6 (54.5%) | 23 (60.5%) | 2 (40.0%) | 11 (45.8%) | 8 (50.0%) | 34 (54.8%) | ||||
A = doxorubicin; C = cyclophosphamide; H = trastuzumab; LVEF = left ventricular ejection fraction; SD = standard deviation; T = paclitaxel; * = In the joint analysis safety population, the median duration of follow-up was 8.1 years for the AC→T + H group and 8.5 years for the AC→T group. | ||||||||||
Following initiation of paclitaxel therapy, 344 patients treated with AC→TH (18.5%) experienced an LVEF percentage decrease of ≥ 10 points from paclitaxel baseline to < 50 points, compared with 82 patients treated with AC→T (7.0%) at a median follow-up of 8.1 years for the AC→TH group. The per patient incidence of new onset cardiac dysfunction, after initiation of paclitaxel therapy, as determined by LVEF, remained unchanged compared to the analysis performed at a median follow up of 2.0 years in the AC→TH group.
An independent clinical review was performed on 62 patients with symptomatic congestive heart failure in the trastuzumab + chemotherapy arm to assess treatment and resolution status. Most patients were treated with oral medications commonly used to manage congestive heart failure. Complete or partial LVEF recovery was documented in 56 patients (90.3%), with complete recovery in 17 of these patients (27.4%) and partial recovery in 39 of these patients (62.9%), compared to 6 patients (9.7%) experiencing no recovery. This analysis also showed evidence of reversibility of left ventricular dysfunction in 64.5% of patients who experienced a symptomatic CHF in the AC→TH group being asymptomatic at the latest follow up.
Risk factors for a cardiac event included trastuzumab treatment, increased age, prior or current use of anti-hypertensive medications and low LVEF prior to or following the initiation of paclitaxel treatment. In the trastuzumab + chemotherapy arm, the risk of a cardiac event increased with the number of these risk factors present. In study B-31, there was no association between the incidence of cardiac events and either radiation to the left side of the chest or smoking.
BCIRG-006
In study BCIRG-006, cardiac events were defined as congestive heart failure (CHF; grade 3 or 4 cardiac left ventricular function [CLVF], per the NCI-CTC, v 2.0), grade 3 or 4 cardiac arrhythmia, grade 3 or 4 cardiac ischemia/infarction, cardiac death and serious adverse events with cardiac etiology not pre-defined as a cardiac event in the protocol but assessed as being a significant cardiac event by the Independent Cardiac Review Panel (ICRP). Asymptomatic LVEF events were defined as an absolute decline in LVEF value of >15 % from baseline to a value that was below the institution’s lower limit of normal (LLN). [Note: asymptomatic LVEF events defined in HERA as: a drop in LVEF of at least 10 EF points from baseline and to below 50%, and in the JA as: absolute drop in LVEF ≥10% to < 55% or an absolute drop in LVEF of ≥5% to below the institution’s LLN.]
Table 11 summarizes symptomatic cardiac events reported at any time during the study.
Table 11 Symptomatic Cardiac Events per the Independent Cardiac Review Panel (ICRP) Occurring at Any Time during the Study (Safety Population) 5 Year Follow Up
| Event Type | AC→T (n = 1041) | AC→TH (n = 1077) | TCH (n = 1056) | |||
|---|---|---|---|---|---|---|
| CHF (Grade 3/4 CLVF) | 6 (0.6%) | 20 (1.9%) | 4 (0.4%) | |||
| Grade 3/4 cardiac ischemia/infarction | 0 | 3 (0.3%) | 2 (0.2%) | |||
| Grade 3/4 arrhythmia | 6 (0.6%) | 3 (0.3%) | 6 (0.6%) | |||
| Cardiac death | 0 | 0 | 0 | |||
| Any symptomatic cardiac event | 10 (1.0%) | 25 (2.3%) | 12 (1.1%) | |||
| AC→T = doxorubicin plus cyclophosphamide, followed by docetaxel; AC→TH = doxorubicin plus cyclophosphamide, followed by docetaxel plus trastuzumab; CHF = congestive heart failure; CLVF = cardiac left ventricular function; TCH = docetaxel, carboplatin, and trastuzumab. | ||||||
At 5.5 years, the rates of symptomatic cardiac or LVEF events were 1.0%, 2.3%, and 1.1% in the AC→T (doxorubicin plus cyclophosphamide, followed by docetaxel), AC→TH (doxorubicin plus cyclophosphamide, followed by docetaxel plus trastuzumab), and TCH (docetaxel, carboplatin and trastuzumab) treatment arms, respectively. For symptomatic CHF (Grade 3 - 4), the 5-year rates were 0.6%, 1.9%, and 0.4% in the AC→T, AC→TH, and TCH treatment arms, respectively. The overall risk of developing symptomatic cardiac events was similar for patients in AC→T and TCH arms. There was an increased risk of developing a symptomatic cardiac event for patients in the AC→TH arm, where the cumulative rate of symptomatic cardiac or LVEF events was 2.3% compared to approximately 1% in the two comparator arms (AC→T and TCH, respectively).
In BCIRG-006 study, 155 patients treated with AC→TH (14.4%) experienced an LVEF decrease of ≥ 10% from baseline to < 50%, compared with 79 (7.6%) patients treated with AC→T and 63 (6.0%) patients treated with TCH.
Table 12 presents the incidence of symptomatic and asymptomatic LVEF events.
Table 12 Asymptomatic and Symptomatic LVEF Declines by Baseline Events, Using the Same Assessment Method as Baseline (Safety Population) 5 Year Follow Up
| Event Type | AC→T (n = 1041) | AC→TH (n = 1077) | TCH (n = 1056) |
|---|---|---|---|
| Absolute decline of >15% from baseline and to a value below the LLN | 50 (4.8%) | 111 (10.3%) | 42 (4.0%) |
| Absolute decline of >10% from baseline and to a value < 50% | 71 (6.8%) | 137 (12.7%) | 50 (4.7%) |
Symptomatic and/or asymptomatic decline of >15%, below the LLN | 56 (5.4%) | 128 (11.9%) | 57 (5.4%) |
| AC-T = doxorubicin plus cyclophosphamide, followed by docetaxel; AC-TH = doxorubicin plus cyclophosphamide, followed by docetaxel plus trastuzumab; ANC = absolute neutrophil count; LLN = lower limit of normal; TCH = docetaxel, carboplatin, and trastuzumab. | |||
Metastatic Breast Cancer (MBC)
HERZUMA® and anthracyclines should not be given concurrently in the MBC setting.
In particular, moderate to severe cardiac dysfunction has been observed in MBC patients treated with trastuzumab in combination with an anthracycline (doxorubicin or epirubicin) and cyclophosphamide (see ADVERSE REACTIONS). The clinical status of patients in the trials who developed congestive heart failure were classified for severity using the New York Heart Association classification system (I-IV1 where IV is the most severe level of cardiac failure).
(See Table 13).
Table 13 Incidence and Severity of Cardiac Dysfunction in Metastatic Breast Cancer Patients
trastuzumab + Anthracycline + cyclophosphamideb | Anthracycline + cyclophosphamideb | trastuzumab + Paclitaxelb | Paclitaxelb | trastuzumaba Alone | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| (n=143) | (n= 135) | (n= 91) | (n= 95) | (n= 338) | |||||||||||
| Any Cardiac Dysfunction | 27% | 7% | 12% | 1% | 4% | ||||||||||
| Class III-IV | 16% | 3% | 2% | 1% | 3% | ||||||||||
a Single agent studies H0551g, H0649g and H0650g. b Randomized Phase III study comparing chemotherapy plus trastuzumab to chemotherapy alone, where chemotherapy is either anthracycline/cyclophosphamide or paclitaxel. | |||||||||||||||
In a subsequent trial with prospective monitoring of cardiac function, the incidence of symptomatic heart failure was 2.2% in patients receiving trastuzumab and docetaxel, compared with 0% in patients receiving docetaxel alone. In the MBC trials, the probability of cardiac dysfunction was highest in patients who received trastuzumab concurrently with anthracyclines. The MBC data suggest that advanced age may increase the probability of cardiac dysfunction.
Pre-existing cardiac disease or prior cardiotoxic therapy (e.g., anthracycline or radiation therapy) to the chest may decrease the ability to tolerate therapy with trastuzumab; however, the data is not adequate to evaluate correlation between cardiac dysfunction observed with trastuzumab and these factors in patients with HER2 positive MBC.
Hematologic
Exacerbation of Chemotherapy-Induced Neutropenia: In randomized, controlled clinical trials in both adjuvant and MBC designed to assess the impact of the addition of trastuzumab on chemotherapy, the per-patient incidences of moderate to severe neutropenia and of febrile neutropenia were higher in patients receiving trastuzumab in combination with myelosuppressive chemotherapy compared with those receiving chemotherapy alone.
Using NCI-CTC criteria, in the adjuvant HERA trial, 0.4% of patients treated with trastuzumab experienced a shift of 3 or 4 grades from baseline, compared with 0.6% in the observation arm.
In the adjuvant studies, NSABP B-31 and NCCTG N9831, there were 6 deaths due to septicemia or severe neutropenia. Five deaths occurred on the chemotherapy alone arm: 2
1 New York Heart Association Functional Classification
Class I: Patients with cardiac disease but without resulting limitations of physical activity. Ordinary physical activity does not cause undue fatigue, palpitation, dyspnea or anginal pain.
Class II: Patients with cardiac disease resulting in slight limitation of physical activity. They are comfortable at rest. Ordinary physical activity results in fatigue, palpitation, dyspnea or anginal pain.
Class III: Patients with cardiac disease resulting in marked limitation of physical activity. They are comfortable at rest. Less than ordinary physical activity causes fatigue, palpitation, dyspnea or anginal pain.
Class IV: Patients with cardiac disease resulting in inability to carry on any physical activity without discomfort. Symptoms of cardiac insufficiency or of the anginal syndrome may be present even at rest. If any physical activity is undertaken, discomfort is increased.
patients died of pneumonia with febrile neutropenia and 3 patients died of septicemia. One death occurred on the trastuzumab + chemotherapy arm and the patient died of infection/neutropenic fever with lung infiltrates. All except 2 septicemia deaths occurred during protocol treatment period.
In the post-market setting in MBC, deaths due to sepsis in patients with severe neutropenia have been reported in patients receiving trastuzumab and myelosuppressive chemotherapy, although in controlled MBC clinical trials (pre- and post-market), the incidence of septic death was not significantly increased.
The pathophysiologic basis for exacerbation of neutropenia has not been determined; the effect of trastuzumab on the pharmacokinetics of chemotherapeutic agents has not been fully evaluated. If neutropenia occurs, the appropriate management should be instituted as per local practice/guidelines and the labelled instructions for chemotherapy agents should be followed with regard to dose interruption or dose reduction (see DOSAGE AND ADMINISTRATION: Recommended Dose and Dosage Adjustment, Dose Reduction).
Hypersensitivity Reactions Including Anaphylaxis, Infusion-Associated Reactions and Pulmonary Events
Administration of HERZUMA® can result in severe hypersensitivity reactions (including anaphylaxis), infusion reactions and pulmonary events. In rare cases, these reactions have been fatal. See discussion below.
There are no data regarding the most appropriate method of identification of patients who may safely be retreated with trastuzumab after experiencing a severe reaction. Trastuzumab has been readministered to some patients who fully recovered from a previous severe reaction. Prior to readministration of trastuzumab the majority of these patients were prophylactically treated with pre-medications including antihistamines and/or corticosteroids. While some of these patients tolerated retreatment, others had severe reactions again despite the use of prophylactic pre-medications.
Hypersensitivity Reactions Including Anaphylaxis: Severe hypersensitivity reactions have been infrequently reported in patients treated with trastuzumab. Signs and symptoms include anaphylaxis, urticaria, bronchospasm, angioedema, and/or hypotension. In some cases, the reactions have been fatal. The onset of symptoms generally occurred during an infusion, but there have also been reports of symptom onset after the completion of an infusion. Reactions were most commonly reported in association with the initial infusion. In HERA 1 observation and 10 trastuzumab treated patients experienced hypersensitivity. Eight out of the 10 events were considered related to trastuzumab treatment. The incidence of allergic reactions in the Joint Analysis (chemotherapy alone versus trastuzumab + chemotherapy: 3.6% versus 3.1% in study B-31 and 1.1% versus 0.3% in study N9831) was comparable between the two treatment arms in both studies. In study BCIRG-006, the incidence of allergic reactions according to the NCI-CTC v 2.0 classification was 9.4%, 12.3% and 14.9% in AC→T, AC→TH and TCH arms, respectively.
Infusional administration of HERZUMA® should be interrupted in all patients with severe hypersensitivity reactions. In the event of a hypersensitivity reaction, appropriate medical therapy should be administered, which may include epinephrine, corticosteroids,
diphenhydramine, bronchodilators, and oxygen. Patients should be evaluated and carefully monitored until complete resolution of signs and symptoms.
Infusion-Related Reactions (IRRs): IRRs are known to occur with trastuzumab. Pre-medication may be used to reduce risk of occurrence of IRRs.
Serious IRRs to infusions of trastuzumab including dyspnea, hypotension, hypertension, wheezing, bronchospasm, tachycardia, reduced oxygen saturation and respiratory distress, supraventricular tachyarrhythmia and urticaria have been reported (see ADVERSE REACTIONS). Patients should be observed for IRRs. Interruption of an IV infusion may help control such symptoms and the infusion may be resumed when symptoms abate. These symptoms can be treated with an analgesic/antipyretic such as meperidine or paracetamol, or an antihistamine such as diphenhydramine. Serious reactions have been treated successfully with supportive therapy such as oxygen, beta-agonists and corticosteroids (see ADVERSE REACTIONS). The appropriate management of patients with uncontrolled hypertension or history of hypertension should be considered prior to infusion with HERZUMA®.
These severe reactions were usually associated with the first infusion of trastuzumab and generally occurred during or immediately following the infusion. For some patients, symptoms later worsened and led to further pulmonary complications. Initial improvement followed by clinical deterioration and delayed reactions with rapid clinical deterioration have also been reported. Fatalities have occurred within hours and up to one week following infusion. On very rare occasions, patients have experienced the onset of infusion symptoms or pulmonary symptoms more than six hours after the start of the infusion of trastuzumab. Patients should be warned of the possibility of such a late onset and should be instructed to contact their physician if those symptoms occur. In rare cases, these reactions are associated with a clinical course culminating in a fatal outcome. Patients who are experiencing dyspnea at rest due to complications of advanced malignancy and comorbidities may be at increased risk of a fatal infusion reaction. Therefore, these patients should not be treated with trastuzumab.
Pulmonary Events: Severe pulmonary events leading to death have been reported with the use of trastuzumab in the adjuvant breast cancer clinical studies and the post-market MBC setting. These events may occur as part of an infusion-related reaction or with a delayed onset (See Infusion-Related Reactions subsection of WARNINGS AND PRECAUTIONS), and were reported to occur at varying latencies, from within 24 hours to over 30 days, since the start of treatment with trastuzumab. Cases of interstitial lung disease (which often present with dyspnea) including lung infiltrates, pneumonitis, pleural effusion, respiratory distress, acute pulmonary edema, respiratory insufficiency, acute respiratory distress syndrome, and pneumonia have been reported. Risk factors associated with interstitial lung disease include prior or concomitant therapy with other anti-neoplastic therapies known to be associated with it such as taxanes, gemcitabine, vinorelbine and radiation therapy. Patients with dyspnea at rest due to complications of advanced malignancy and co-morbidities may be at increased risk of pulmonary events. Therefore, these patients should not be treated with HERZUMA®.
Other severe events reported rarely in the post-market MBC setting include pneumonitis and pulmonary fibrosis. All of the confirmed cases of pulmonary fibrosis received to date are characterized by one or more significant confounding factors including pre-existing lung disease and prior/concomitant chemotherapy such as cyclophosphamide. However, a causal relationship between trastuzumab and pulmonary fibrosis cannot be excluded.
Immune
Immunogenicity:
Samples for assessment of human anti-human antibody (HAHA) were not collected in studies of adjuvant breast cancer. Of 903 patients that have been evaluated in the MBC trials, human anti-human antibody (HAHA) to trastuzumab was detected in 1 patient, who had no allergic manifestations.
Respiratory
Refer to Pulmonary Events subsection of WARNINGS AND PRECAUTIONS.
Thrombosis/Embolism
Thrombosis/embolism has been observed in patients who receive trastuzumab + chemotherapy in both the adjuvant and metastatic treatment setting, and in rare cases, has been fatal (see ADVERSE REACTIONS section).
Ability to Drive and Use Machines
Trastuzumab has a minor influence on the ability to drive and use machines. Dizziness and somnolence may occur during treatment with HERZUMA®. Patients experiencing infusion-related symptoms should be advised not to drive or use machines until symptoms resolve completely.
Selection of Patients / Diagnostic Tests
Early Breast Cancer (EBC)/Metastatic Breast Cancer (MBC)
HERZUMA® should only be used in patients whose tumours overexpress HER2 as determined by immunohistochemistry. CICH or FISH testing for HER2 status also may be used, provided that the testing is done in experienced laboratories that have validated the test.
To ensure accurate and reproducible results, the protocol described in the package insert of an appropriate diagnostic test needs to be strictly followed. However, based on the current scientific knowledge, no standard test can be recommended at this time. There is no standard method of staining and no standard for the type of antibodies used. The grading for overexpression is subjective, and the signal may fade with time on stored slides.
The test method for HER2 overexpression used to determine eligibility of patients for inclusion in the MBC clinical trials employed immunohistochemical staining for HER2 of fixed material from tissue biopsy using the murine monoclonal antibodies CB11 and 4D5. Patients classified as staining 2+ or 3+ were included, while those staining 0 or 1+ were excluded. Greater than 70% of patients enrolled exhibited 3+ overexpression. The data suggest that beneficial effects were greater among those patients with higher levels of overexpression of HER2.
In the studies, an investigative clinical trial assay was employed which utilized a 0 to 3+ scale. The degree of HER2 overexpression indicated by different test methods may not correlate with that used as the eligibility criterion for inclusion in the clinical trials. For example, a validated IHC assay utilizes a scale of 0 to 3+. A reading of 3+ with the validated IHC assay is likely to correspond to that of a 2+ or 3+ with the investigative clinical trial assay. A 2+ reading with the validated IHC assay would likely incorporate a significant number of patients who were scored as 1+ by the investigative clinical trial assay. These patients (1+) would not have met the inclusion criteria. Test methods having increased sensitivity, relative to the investigative clinical trial assay, may alter the benefit-to-risk ratio compared to that seen in the clinical trials. In deciding which patients should receive HERZUMA®, the risk of cardiac dysfunction (see WARNINGS and PRECAUTIONS) must be weighed against the potential benefits of treatment, especially for those not in the high range of HER2 overexpression.
For inclusion criteria in terms of HER2 expression in clinical trials in EBC see Clinical Trials -Reference Biologic Drug section.
Metastatic Gastric Cancer (MGC)
HERZUMA® should only be administered to patients with MGC whose tumours have HER2 overexpression as determined by validated immunohistochemistry (IHC) and fluorescent in situ hybridization (FISH) testing. The testing should be done in experienced laboratories that have validated the test.
Patients are eligible for HERZUMA® treatment if they demonstrate strong HER2 protein overexpression, defined by a 3+ score by IHC, or a 2+ score by IHC and a positive FISH result.
8.1 Special Populations
8.1.1 Women and Men of Reproductive Potential:
Fertility
It is not known whether HERZUMA® can affect reproductive capacity. Animal reproduction studies revealed no evidence of impaired fertility or harm to the foetus (see NON-CLINICAL TOXICOLOGY – REFERENCE BIOLOGIC DRUG, Reproductive Toxicity).
Contraception
Women of childbearing potential should be advised to use effective contraception during treatment with HERZUMA® and for at least 7 months after treatment has concluded (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics)
8.1.2 Pregnant Women
Reproduction studies have been conducted in cynomolgus monkeys at doses up to 25 times the weekly human maintenance dose of 2 mg/kg trastuzumab and have revealed no evidence of impaired fertility or harm to the fetus (see NON-CLINICAL TOXICOLOGY – REFERENCE BIOLOGIC DRUG, Reproductive Toxicity). However, when assessing the risk of reproductive toxicity in humans, it is important to consider the significance of the rodent form of the HER2 receptor in normal embryonic development and the embryonic death in mutant mice lacking this receptor. Placental transfer of trastuzumab during the early (days 20-50 of gestation) and late (days 120-150 of gestation) fetal development period was observed.
HERZUMA® can cause fetal harm when administered to a pregnant woman. In the post-market setting, cases of impairment of fetal renal growth and/or renal function impairment, intrauterine growth retardation and skeletal abnormalities in association with oligohydramnios during the second and third trimesters, some associated with fatal pulmonary hypoplasia of the fetus, have been reported in pregnant women receiving trastuzumab. Also, the causal role of trastuzumab cannot be excluded nor confirmed in two cases of interventricular septal defects reported in infants exposed to trastuzumab in utero. In one of these two cases, spontaneous closure of the defect occurred nine months postpartum. No follow up information regarding closure of the defect was available in the second case. HER2 is known to be expressed in many embryonic tissues. Women who become pregnant should be advised of the possibility of harm to the fetus. If a pregnant woman is treated with HERZUMA®, close monitoring by a multidisciplinary team is desirable.
Women using HERZUMA® during pregnancy should be monitored for oligohydramnios. If oligohydramnios occurs, fetal testing should be done that is appropriate for gestational age and consistent with community standards of care. Additional intravenous (IV) hydration has been helpful when oligohydramnios has occurred following administration of other chemotherapy agents; however, the effects of additional IV hydration with trastuzumab treatment are not known.
Animal reproduction studies revealed no evidence of impaired fertility or harm to the fetus. Because animal reproduction studies are not always predictive of human response, HERZUMA® should not be used during pregnancy unless the potential benefit for the mother outweighs the potential risk to the fetus.
8.1.3 Breast-feeding
A study conducted in cynomolgus monkeys at doses 25 times the weekly human maintenance dose of 2 mg/kg trastuzumab from days 120 to 150 of pregnancy demonstrated that trastuzumab is secreted in the milk postpartum. The exposure to trastuzumab in utero and the presence of trastuzumab in the serum of infant monkeys was not associated with any adverse effects on their growth or development from birth to 1 month of age. It is not known whether trastuzumab is excreted in human milk. As human IgG is excreted in human milk, and the potential for absorption and harm to the infant is unknown, a decision should be made whether to discontinue nursing, or discontinue drug, taking into account the elimination half-life of trastuzumab and the importance of the drug to the mother.
8.1.4 Pediatrics
The safety and effectiveness of trastuzumab in pediatric patients below the age of 18, have not been established.
8.1.5 Geriatrics (> 65 years of age)
Trastuzumab has been administered in clinical studies to 386 patients who were 65 years of age or over (253 in the adjuvant treatment and 133 in MBC treatment settings). The risk of cardiac dysfunction was increased in geriatric patients as compared to younger patients in both those receiving treatment for metastatic disease and those receiving adjuvant therapy in studies NSABP B-31 and NCCTG N9831, and BCIRG-006. Age ≥ 60 years was associated with increased risk of shorter time to first symptomatic cardiac event in study BCIRG-006 (based on 35 cardiac events in 2066 patients) (for the definition of cardiac events in each study see
WARNINGS AND PRECAUTIONS, Cardiotoxicity, Early Breast Cancer). Limitations in data collection and differences in study design of the 4 studies of trastuzumab in adjuvant treatment of breast cancer preclude a determination of whether the toxicity profile of trastuzumab in older patients is different from younger patients. The reported clinical experience is not adequate to determine whether the efficacy improvements (as measured by ORR, TTP, OS, and DFS) of trastuzumab treatment in older patients differ from those observed in patients <65 years of age, for either treatment of metastatic disease or adjuvant treatment of EBC.
In ToGA (BO18255) study in MGC, of the 294 patients treated with trastuzumab, 108 (37%) were 65 years of age or older, while 13 (4.4%) were 75 and over. No overall differences in safety or effectiveness were observed.
The risk of hematologic toxicities (leukopenia and thrombocytopenia) may be increased in geriatric patients.
Data suggest that the disposition of trastuzumab is not altered based on age (see ACTION AND CLINICAL PHARMACOLOGY: Pharmacokinetics). In clinical studies, geriatric patients (≥ 65 years of age) did not receive reduced doses of trastuzumab.
9 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared HERZUMA® to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
9.1 Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Early Breast Cancer (EBC)
HERA
(adjuvant sequential: use of trastuzumab following surgery and after chemotherapy)
Please see WARNINGS AND PRECAUTIONS: Cardiovascular/Cardiotoxicity/Early Breast Cancer – Table 5~8 for a description of the absolute numbers and rates of cardiac endpoints in HERA as well as the median time to return to baseline LVEF/ stabilizations of LVEF in the HERA trial.
The HERA trial is a randomized, open label study in patients with HER2 positive EBC. Table 14 displays adverse events which were reported after 8 years of median follow up in ≥ 1% of patients, by study treatment.
Table 14 Adverse Events Reported in ≥ 1% of HERA Study Patients, by Study Treatment Final Analysis After 8 years of Median Follow Up According to MedDRA v 15.0 Classification
| Adverse Event Term | Observation Only | trastuzumab |
|---|---|---|
| 1 year | ||
| N = 1744 | N = 1682 | |
| No. (%) | No. (%) | |
| Blood and Lymphatic System Disorders | ||
| Anemia | 4 (<1) | 15 (<1) |
| Cardiac Disorders | ||
| Cardiac Failure Congestive | 19 (1) | 93 (6)* |
| Palpitations | 20 (1) | 73 (4) |
| Tachycardia | 5 (<1) | 25 (1) |
| Ear and Labyrinth Disorders | ||
| Vertigo | 14 (<1) | 33 (2) |
| Tinnitus | 6 (<1) | 7 (<1) |
| Eye Disorders | ||
| Conjunctivitis | 7 (<1) | 21 (1) |
| Vision blurred | 6 (<1) | 16 (<1) |
| Lacrimation Increased | 1 (<1) | 12 (<1) |
| Gastrointestinal Disorders | ||
| Diarrhea | 23 (1) | 156 (9) |
| Nausea | 37 (2) | 134 (8) |
| Vomiting | 17 (<1) | 76 (5) |
| Constipation | 27 (2) | 55 (3) |
| Abdominal Pain | 25 (1) | 60 (4) |
| Abdominal Pain Upper | 30 (2) | 45 (3) |
| Dyspepsia | 14 (<1) | 42 (2) |
| Stomatitis | 1 (<1) | 33 (2) |
| Gastritis | 17 (<1) | 27 (2) |
| Hemorrhoids | 8 (<1) | 18 (1) |
| Mouth Ulceration | 2 (<1) | 13 (<1) |
| General Disorders and Administration Site Conditions | ||
| Fatigue | 83 (5) | 198 (12) |
| Edema Peripheral | 64 (4) | 114 (7) |
| Pyrexia | 12 (<1) | 119 (7) |
| Asthenia | 42 (2) | 102 (6) |
| Chills | 1 (<1) | 101 (6) |
| Chest Pain | 36 (2) | 65 (4) |
| Influenza Like Illness | 7 (<1) | 51 (3) |
| Pain | 24 (1) | 23 (1) |
| Spinal Pain | 21 (1) | 21 (1) |
| Chest Discomfort | 6 (<1) | 27 (2) |
| Axillary Pain | 17 (<1) | 18 (1) |
| Edema | 10 (<1) | 23 (1) |
| Mucosal Inflammation | 1 (<1) | 18 (1) |
| Malaise | 1 (<1) | 18 (1) |
| Immune System Disorders | ||
| Seasonal Allergy | 6 (<1) | 14 (<1) |
| Infections and Infestations# | ||
| Nasopharyngitis | 65 (4) | 192 (11) |
| Influenza | 17 (<1) | 95 (6) |
| Upper Respiratory Tract Inflection | 31 (2) | 53 (3) |
| Urinary Tract Infection | 19 (1) | 54 (3) |
| Rhinitis | 11 (<1) | 44 (3) |
| Bronchitis | 25 (1) | 36 (2) |
| Cystitis | 15 (<1) | 28 (2) |
| Adverse Event Term | Observation Only | trastuzumab |
|---|---|---|
| 1 year | ||
| N = 1744 | N = 1682 | |
| No. (%) | No. (%) | |
| Sinusitis | 7 (<1) | 36 (2) |
| Pharyngitis | 12 (<1) | 33 (2) |
| Herpes Zoster | 14 (<1) | 31 (2) |
| Lower Respiratory Tract Infection | 14 (<1) | 17 (1) |
| Gastroenteritis | 10 (<1) | 9 (<1) |
| Oral Herpes | 5 (<1) | 15 (<1) |
| Cellulitis | 6 (<1) | 14 (<1) |
| Vaginal Infection | 10 (<1) | 13 (<1) |
| Ear Infection | 6 (<1) | 9 (<1) |
| Localised Infection | - | 18 (1) |
| Injury, Poisoning and Procedural Complications | ||
| Confusion | 12 (<1) | 13 (<1) |
| Investigations | ||
| Ejection Fraction Decreased | 11 (<1) | 64 (4) |
| Weight Increased | 23 (1) | 42 (2) |
| Weight Decreased | 10 (<1) | 10 (<1) |
| Metabolism and Nutrition Disorders | ||
| Decreased Appetite | 17 (<1) | 25 (1) |
| Hypercholesterolemia | 15 (<1) | 16 (<1) |
| Musculoskeletal and Connective Tissue Disorders | ||
| Arthralgia | 148 (8) | 223 (13) |
| Back Pain | 105 (6) | 145 (9) |
| Pain in Extremity | 73 (4) | 94 (6) |
| Musculoskeletal Pain | 66 (4) | 75 (4) |
| Myalgia | 28 (2) | 86 (5) |
| Muscle Spasms | 13 (<1) | 68 (4) |
| Bone Pain | 31 (2) | 54 (3) |
| Musculoskeletal Chest Pain | 37 (2) | 43 (3) |
| Osteoporosis | 29 (2) | 30 (2) |
| Neck Pain | 18 (1) | 29 (2) |
| Osteoarthritis | 18 (1) | 28 (2) |
| Osteopenia | 12 (<1) | 19 (1) |
| Musculoskeletal Stiffness | 8 (<1) | 14 (<1) |
| Neoplasms Benign, Malignant and Unspecified (Incl Cysts And Polyps) | ||
| Contralateral Breast Cancer | 10 (<1) | 23 (1) |
| Uterine Letomyoma | 7 (<1) | 9 (<1) |
| Nervous System Disorders | ||
| Headache | 73 (4) | 199 (12) |
| Dizziness | 39 (2) | 80 (5) |
| Paraesthesia | 21 (1) | 42 (2) |
| Hypoaesthesia | 15 (<1) | 25 (1) |
| Lethargy | 8 (<1) | 20 (1) |
| Migraine | 3 (<1) | 15 (<1) |
| Peripheral Sensory Neuropathy | 6 (<1) | 14 (<1) |
| Pregnancy, Puerperium and Perinatal Conditions | ||
| Pregnancy | 11 (<1) | 22 (1) |
| Psychiatric Disorders | ||
| Depression | 59 (3) | 87 (5) |
| Insomnia | 49 (3) | 94 (6) |
| Anxiety | 32 (2) | 56 (3) |
| Sleep Disorder | 5 (<1) | 13 (<1) |
| Renal and Urinary Disorders | ||
| Dysuria | 3 (<1) | 20 (1) |
| Adverse Event Term | Observation Only | trastuzumab |
|---|---|---|
| 1 year | ||
| N = 1744 | N = 1682 | |
| No. (%) | No. (%) | |
| Reproductive System and Breast Disorders | ||
| Breast Pain | 26 (1) | 36 (2) |
| Vaginal Haemorrhage | 20 (1) | 23 (1) |
| Vulvovaginal Dryness | 16 (<1) | 23 (1) |
| Breast Mass | 22 (1) | 17 (1) |
| Vaginal Discharge | 9 (<1) | 15 (<1) |
| Endometrial Hyperplasia | 13 (<1) | 17 (1) |
| Respiratory, Thoracic and Mediastinal Disorders | ||
| Cough | 61 (3) | 116 (7) |
| Dyspnea | 46 (3) | 81 (5) |
| Oropharnygeal Pain | 14 (<1) | 40 (2) |
| Epistaxis | 3 (<1) | 29 (2) |
| Dyspnea Exertional | 16 (<1) | 32 (2) |
| Rhinorrhoea | 5 (<1) | 27 (2) |
| Nasal Dryness | 1 (<1) | 25 (1) |
| Asthma | 7 (<1) | 9 (<1) |
| Skin and Subcutaneous Tissue Disorders | ||
| Rash | 25 (1) | 98 (6) |
| Onychoclasis | 2 (<1) | 53 (3) |
| Nail Disorder | 2 (<1) | 52 (3) |
| Pruritus | 14 (<1) | 58 (3) |
| Dry Skin | 4 (<1) | 22 (1) |
| Erythema | 8 (<1) | 39 (2) |
| Alopecia | 6 (<1) | 18 (1) |
| Scar Pain | 18 (1) | 21 (1) |
| Eczema | 9 (<1) | 19 (1) |
| Hyperhidrosis | 10 (<1) | 17 (1) |
| Urticaria | 4 (<1) | 13 (<1) |
| Acne | 3 (<1) | 17 (1) |
| Vascular Disorders | ||
| Hot Flush | 129 (7) | 163 (10) |
| Hypertension | 61 (3) | 104 (6) |
| Lymphoedema | 69 (4) | 80 (5) |
| Flushing | 10 (<1) | 14 (<1) |
| Hypotension | 4 (<1) | 14 (<1) |
Multiple occurrences of the same adverse even in one individual counted only once. * 69 out of the total 93 Cardiac Failure Congestive events reported in the 1-year trastuzumab arm occurred within 365 days from randomization. # Serious adverse reactions of cellulitis and erysipelas were also reported in the HERA study. | ||
In HERA, after a median follow-up of 12 months, 1 observation and 10 trastuzumab treated patients experienced hypersensitivity. Eight out of the 10 events were considered related to trastuzumab treatment.
In total, in the trastuzumab 1 year arm, 124 patients (7%) withdrew from trastuzumab treatment due to adverse events, and 2 patients (<1%) withdrew from the post-treatment follow-up phase due to adverse events, based on the withdrawal criteria in the HERA study protocol.
Please see
Table 7 and
Table 8 in WARNINGS AND PRECAUTIONS: Cardiovascular, Cardiotoxicity, Early Breast Cancer for information on the median time to return to baseline LVEF and stabilizations of LVEF after 8 years of median follow up in the HERA trial.
Joint Analysis –NSABP Study B-31 and NCCTG Study N9831
(adjuvant concurrent: use of trastuzumab in combination with paclitaxel)
Cardiac failure/dysfunction, pulmonary events, and exacerbation of chemotherapy-induced neutropenia were the most serious adverse reactions in the two randomized, controlled adjuvant breast cancer studies (NSABP study B-31 and NCCTG study N9831, see CLINICAL STUDIES). Please refer to WARNINGS AND PRECAUTIONS section for detailed description of these reactions and for a description of the incidence and type of cardiac events seen in the Joint Analysis.
Adverse events according to the National Cancer Institute - Common Terminology Criteria NCI-CTC v 2.0 classification occurring at a frequency of ≥ 1% for NSABP-B31 and NCCTG N9831, are summarized in Table 15 and
Table 16 respectively.
Table 15 Adverse Events of Any Grade with Incidence ≥ 1% in Study B-31 (Final Analysis after Median Follow-up of 8.1 years in the AC - T+H Group) According to NCI-CTC v 2.0 Classification
| Adverse Event Term a | AC - T (n = 885) | AC - T + H (n = 1030) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Any Grade | Grades 3–4 | Grade 5 | Any Grade | Grades 3–4 | Grade 5 | |||||||||
| Allergy/immunology | ||||||||||||||
| Allergic reaction* | 33 (3.7%) | 10 (1.1%) | (0.0%) | 35 (3.4%) | 12 (1.2%) | (0.0%) | ||||||||
| Allergic rhinitis | 11 (1.2%) | (0.0%) | (0.0%) | 29 (2.8%) | (0.0%) | (0.0%) | ||||||||
| Blood/bone marrow | ||||||||||||||
| Hemoglobin (HGB)* | 156 (17.6%) | 27 (3.1%) | (0.0%) | 209 (20.3%) | 33 (3.2%) | (0.0%) | ||||||||
| Leukocytes (total WBC) | 152 (17.2%) | 95 (10.7%) | (0.0%) | 201 (19.5%) | 103 (10.0%) | (0.0%) | ||||||||
| Lymphopenia | 43 (4.9%) | 27 (3.1%) | (0.0%) | 54 (5.2%) | 31 (3.0%) | (0.0%) | ||||||||
| Neutrophils/granulocytes | 112 (12.7%) | 88 (9.9%) | (0.0%) | 134 (13.0%) | 107 (10.4%) | (0.0%) | ||||||||
| Platelets | 22 (2.5%) | 11 (1.2%) | (0.0%) | 23 (2.2%) | 12 (1.2%) | (0.0%) | ||||||||
| Cardiovascular (general) | ||||||||||||||
| Cardiac-left ventricular function* | 47 (5.3%) | 7 (0.8%) | (0.0%) | 151 (14.7%) | 35 (3.4%) | (0.0%) | ||||||||
| Edema | 26 (2.9%) | 1 (0.1%) | (0.0%) | 50 (4.9%) | (0.0%) | (0.0%) | ||||||||
| Hypertension | 6 (0.7%) | 4 (0.5%) | (0.0%) | 25 (2.4%) | 17 (1.7%) | (0.0%) | ||||||||
| Thrombosis/embolism* | 24 (2.7%) | 23 (2.6%) | (0.0%) | 39 (3.8%) | 35 (3.4%) | (0.0%) | ||||||||
| Constitutional symptoms | ||||||||||||||
| Fatigue* | 323 (36.5%) | 54 (6.1%) | (0.0%) | 426 (41.4%) | 58 (5.6%) | (0.0%) | ||||||||
| Fever (in the absence of neutropenia)* | 21 (2.4%) | 2 (0.2%) | (0.0%) | 38 (3.7%) | 7 (0.7%) | (0.0%) | ||||||||
| Sweating (diaphoresis) | 10 (1.1%) | (0.0%) | (0.0%) | 19 (1.8%) | (0.0%) | (0.0%) | ||||||||
| Weight gain | 5 (0.6%) | 1 (0.1%) | (0.0%) | 14 (1.4%) | 3 (0.3%) | (0.0%) | ||||||||
| Dermatology/skin | ||||||||||||||
| Alopecia | 285 (32.2%) | 3 (0.3%) | (0.0%) | 354 (34.4%) | 2 (0.2%) | (0.0%) | ||||||||
| Nail changes | 10 (1.1%) | (0.0%) | (0.0%) | 30 (2.9%) | 1 (0.1%) | (0.0%) | ||||||||
| Pruritus | 18 (2.0%) | 1 (0.1%) | (0.0%) | 18 (1.7%) | 3 (0.3%) | (0.0%) | ||||||||
| Radiation dermatitis | 20 (2.3%) | 3 (0.3%) | (0.0%) | 31 (3.0%) | 10 (1.0%) | (0.0%) | ||||||||
| Rash/desquamation* | 88 (9.9%) | 12 (1.4%) | (0.0%) | 130 (12.6%) | 6 (0.6%) | (0.0%) | ||||||||
| Skin-other | 14 (1.6%) | 2 (0.2%) | (0.0%) | 25 (2.4%) | 2 (0.2%) | (0.0%) | ||||||||
| Wound-infectious | 7 (0.8%) | 4 (0.5%) | (0.0%) | 15 (1.5%) | 8 (0.8%) | (0.0%) | ||||||||
| Adverse Event Term a | AC - T (n = 885) | AC - T + H (n = 1030) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Any Grade | Grades 3–4 | Grade 5 | Any Grade | Grades 3–4 | Grade 5 | |||||||||
| Endocrine | ||||||||||||||
| Hot flashes/flushes | 157 (17.7%) | 2 (0.2%) | (0.0%) | 197 (19.1%) | (0.0%) | (0.0%) | ||||||||
| Gastrointestinal | ||||||||||||||
| Anorexia* | 71 (8.0%) | 12 (1.4%) | (0.0%) | 64 (6.2%) | 11 (1.1%) | (0.0%) | ||||||||
| Constipation* | 81 (9.2%) | 7 (0.8%) | (0.0%) | 123 (11.9%) | 5 (0.5%) | (0.0%) | ||||||||
| Dehydration | 22 (2.5%) | 7 (0.8%) | (0.0%) | 28 (2.7%) | 5 (0.5%) | (0.0%) | ||||||||
| Diarrhea without prior colostomy* | 83 (9.4%) | 23 (2.6%) | (0.0%) | 112 (10.9%) | 26 (2.5%) | (0.0%) | ||||||||
| Dyspepsia | 46 (5.2%) | 2 (0.2%) | (0.0%) | 51 (5.0%) | 2 (0.2%) | (0.0%) | ||||||||
| GI-other | 14 (1.6%) | 2 (0.2%) | (0.0%) | 24 (2.3%) | 4 (0.4%) | (0.0%) | ||||||||
| Nausea* | 309 (34.9%) | 70 (7.9%) | (0.0%) | 356 (34.6%) | 69 (6.7%) | (0.0%) | ||||||||
| Stomatitis/pharyngitis* | 151 (17.1%) | 6 (0.7%) | (0.0%) | 179 (17.4%) | 10 (1.0%) | (0.0%) | ||||||||
| Taste disturbance (dysgeusia) | 13 (1.5%) | (0.0%) | (0.0%) | 25 (2.4%) | (0.0%) | (0.0%) | ||||||||
| Vomiting* | 232 (26.2%) | 66 (7.5%) | (0.0%) | 247 (24.0%) | 64 (6.2%) | (0.0%) | ||||||||
| Hemorrhage | ||||||||||||||
| Vaginal bleeding | 4 (0.5%) | (0.0%) | (0.0%) | 18 (1.8%) | (0.0%) | (0.0%) | ||||||||
| Hepatic | ||||||||||||||
| SGOT (AST) (serum glutamic oxaloacetic transaminase)* | 18 (2.0%) | 6 (0.7%) | (0.0%) | 27 (2.6%) | 5 (0.5%) | (0.0%) | ||||||||
| SGPT (ALT) serum glutamic pyruvic transaminase * | 26 (2.9%) | 5 (0.6%) | (0.0%) | 33 (3.2%) | 5 (0.5%) | (0.0%) | ||||||||
| Infection/febrile neutropenia | ||||||||||||||
| Febrile neutropenia* | 42 (4.7%) | 42 (4.7%) | (0.0%) | 39 (3.8%) | 39 (3.8%) | (0.0%) | ||||||||
| Infection* | 246 (27.8%) | 124 (14.0%) | 3 (0.3%) | 341 (33.1%) | 140 (13.6%) | (0.0%) | ||||||||
| Lymphatics | ||||||||||||||
| Lymphatics | 9 (1.0%) | (0.0%) | (0.0%) | 25 (2.4%) | (0.0%) | (0.0%) | ||||||||
| Metabolic/laboratory | ||||||||||||||
| Hyperglycemia | 118 (13.3%) | 46 (5.2%) | (0.0%) | 139 (13.5%) | 49 (4.8%) | (0.0%) | ||||||||
| Hypoglycemia | 6 (0.7%) | 2 (0.2%) | (0.0%) | 12 (1.2%) | 6 (0.6%) | (0.0%) | ||||||||
| Musculoskeletal | ||||||||||||||
| Joint, muscle, bone-other | 11 (1.2%) | 2 (0.2%) | (0.0%) | 19 (1.8%) | 2 (0.2%) | (0.0%) | ||||||||
| Neurology | ||||||||||||||
| Ataxia (incoordination) | 1 (0.1%) | (0.0%) | (0.0%) | 11 (1.1%) | 2 (0.2%) | (0.0%) | ||||||||
| Dizziness/lightheadedness | 30 (3.4%) | 5 (0.6%) | (0.0%) | 36 (3.5%) | 6 (0.6%) | (0.0%) | ||||||||
| Insomnia | 35 (4.0%) | 2 (0.2%) | (0.0%) | 60 (5.8%) | 6 (0.6%) | (0.0%) | ||||||||
| Mood alteration-anxiety/agitation | 44 (5.0%) | 5 (0.6%) | (0.0%) | 46 (4.5%) | 9 (0.9%) | (0.0%) | ||||||||
| Mood alteration-depression | 56 (6.3%) | 10 (1.1%) | (0.0%) | 71 (6.9%) | 11 (1.1%) | (0.0%) | ||||||||
| Neuropathy-motor* | 45 (5.1%) | 17 (1.9%) | (0.0%) | 51 (5.0%) | 16 (1.6%) | (0.0%) | ||||||||
| Neuropathy-sensory* | 203 (22.9%) | 59 (6.7%) | (0.0%) | 235 (22.8%) | 43 (4.2%) | (0.0%) | ||||||||
| Syncope (fainting) | 8 (0.9%) | 8 (0.9%) | (0.0%) | 12 (1.2%) | 12 (1.2%) | (0.0%) | ||||||||
| Ocular/visual | ||||||||||||||
| Dry Eye | 13 (1.5%) | (0.0%) | (0.0%) | 9 (0.9%) | (0.0%) | (0.0%) | ||||||||
| Tearing (watery eyes) | 6 (0.7%) | (0.0%) | (0.0%) | 12 (1.2%) | (0.0%) | (0.0%) | ||||||||
| Vision-blurred vision | 11 (1.2%) | (0.0%) | (0.0%) | 22 (2.1%) | (0.0%) | (0.0%) | ||||||||
| Pain | ||||||||||||||
| Abdominal pain or cramping | 25 (2.8%) | 12 (1.4%) | (0.0%) | 24 (2.3%) | 6 (0.6%) | (0.0%) | ||||||||
| Arthralgia (joint pain)* | 273 (30.8%) | 57 (6.4%) | (0.0%) | 329 (31.9%) | 68 (6.6%) | (0.0%) | ||||||||
| Bone pain | 46 (5.2%) | 14 (1.6%) | (0.0%) | 60 (5.8%) | 11 (1.1%) | (0.0%) | ||||||||
| Chest pain | 14 (1.6%) | 4 (0.5%) | (0.0%) | 36 (3.5%) | 4 (0.4%) | (0.0%) | ||||||||
| Headache* | 80 (9.0%) | 20 (2.3%) | (0.0%) | 127 (12.3%) | 30 (2.9%) | (0.0%) | ||||||||
| Myalgia (muscle pain)* | 293 (33.1%) | 83 (9.4%) | (0.0%) | 362 (35.1%) | 65 (6.3%) | (0.0%) | ||||||||
| Neuropathic pain | 11 (1.2%) | 4 (0.5%) | (0.0%) | 20 (1.9%) | 6 (0.6%) | (0.0%) | ||||||||
| Pain-other | 50 (5.6%) | 10 (1.1%) | (0.0%) | 78 (7.6%) | 10 (1.0%) | (0.0%) | ||||||||
| Pulmonary | ||||||||||||||
| Cough | 9 (1.0%) | 1 (0.1%) | (0.0%) | 32 (3.0%) | 2 (0.2%) | (0.0%) | ||||||||
| Adverse Event Term a | AC - T (n = 885) | AC - T + H (n = 1030) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Any Grade | Grades 3–4 | Grade 5 | Any Grade | Grades 3–4 | Grade 5 | ||||||||
| Dyspnea (shortness of breath) | 63 (7.1%) | 21 (2.4%) | (0.0%) | 144 (14.0%) | 24 (2.3%) | (0.0%) | |||||||
| Pulmonary-other | 7 (0.8%) | 3 (0.3%) | (0.0%) | 15 (1.5%) | 4 (0.4%) | (0.0%) | |||||||
| Renal/genitourinary | |||||||||||||
| Dysuria (painful urination) | 9 (1.0%) | 1 (0.1%) | (0.0%) | 11 (1.1%) | 1 (0.1%) | (0.0%) | |||||||
| Urinary frequency/urgency | 7 (0.8%) | 3 (0.3%) | (0.0%) | 11 (1.1%) | 2 (0.2%) | (0.0%) | |||||||
| Vaginitis (not due to infection) | 10 (1.1%) | 1 (0.1%) | (0.0%) | 4 (0.4%) | 1 (0.1%) | (0.0%) | |||||||
| Sexual/reproductive function | |||||||||||||
| Irregular menses (change from baseline) | 35 (4.0%) | 27 (3.1%) | (0.0%) | 44 (4.3%) | 37 (3.6%) | (0.0%) | |||||||
| Vaginal dryness | 12 (1.4%) | (0.0%) | (0.0%) | 26 (2.5%) | 1 (0.1%) | (0.0%) | |||||||
a NCIC CTC terminology A = doxorubicin; C = cyclophosphamide; GI = gastrointestinal; H = trastuzumab; T = paclitaxel; WBC = white blood cell. Note: Only Grade 3–5 events, treatment-related Grade 2 events, Grade 2–5 cardiac left ventricular dysfunction, and Grade 2–5 dyspnea were collected during and 3 months following protocol treatment. The term “febrile neutropenia” refers to febrile neutropenia with no evidence of infection; decreased neutrophils were not intended to be collected. * Adverse event term is itemized on the Adverse Event CRF. | |||||||||||||
Table 16 Adverse Events of Any Grade with Incidence ≥ 1% in Study N9831 (Final Analysis after Median Follow-up of 8.1 years in the AC - T+H Group) According to NCI-CTC v 2.0 Classification
| Adverse Event Term a | AC - T (n = 766) | AC - T + H (n = 969) | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Any Grade | Grades 3–4 | Grade 5 | Any Grade | Grades 3–4 | Grade 5 | |||||||||||
| Allergy/immunology | ||||||||||||||||
| Allergic reaction* | 9 (1.2%) | 9 (1.2%) | (0.0%) | 3 (0.3%) | 3 (0.3%) | (0.0%) | ||||||||||
| Blood/bone marrow | ||||||||||||||||
| Leukocytes (total WBC)* | 59 (7.7%) | 58 (7.6%) | 1 (0.1%) | 82 (8.5%) | 82 (8.5%) | (0.0%) | ||||||||||
| Neutrophils/granulocytes* | 209 (27.3%) | 208 (27.2%) | 1 (0.1%) | 286 (29.5%) | 286 (29.5%) | (0.0%) | ||||||||||
| Cardiovascular (arrhythmia) | ||||||||||||||||
| Palpitations | 12 (1.6%) | (0.0%) | (0.0%) | 15 (1.5%) | (0.0%) | (0.0%) | ||||||||||
| Cardiovascular (general) | ||||||||||||||||
| Cardiac-ischemia/infarction* | 9 (1.2%) | 7 (0.9%) | (0.0%) | 13 (1.3%) | 7 (0.7%) | (0.0%) | ||||||||||
| Cardiac-left ventricular function* | 73 (9.5%) | 1 (0.1%) | (0.0%) | 219 (22.6%) | 21 (2.2%) | (0.0%) | ||||||||||
| Edema | 8 (1.0%) | (0.0%) | (0.0%) | 15 (1.5%) | (0.0%) | (0.0%) | ||||||||||
| Hypertension | 7 (0.9%) | 3 (0.4%) | (0.0%) | 12 (1.2%) | 6 (0.6%) | (0.0%) | ||||||||||
| Thrombosis/embolism* | 22 (2.9%) | 20 (2.6%) | 2 (0.3%) | 18 (1.9%) | 18 (1.9%) | (0.0%) | ||||||||||
| Constitutional symptoms | ||||||||||||||||
| Fatigue* | 34 (4.4%) | 34 (4.4%) | (0.0%) | 41 (4.2%) | 41 (4.2%) | (0.0%) | ||||||||||
| Dermatology/skin | ||||||||||||||||
| Nail changes* | 50 (6.5%) | (0.0%) | (0.0%) | 116 (12.0%) | (0.0%) | (0.0%) | ||||||||||
| Gastrointestinal | ||||||||||||||||
| Diarrhea without prior colostomy* | 5 (0.7%) | 5 (0.7%) | (0.0%) | 33 (3.4%) | 33 (3.4%) | (0.0%) | ||||||||||
| Nausea* | 40 (5.2%) | 40 (5.2%) | (0.0%) | 53 (5.5%) | 53 (5.5%) | (0.0%) | ||||||||||
| Vomiting* | 39 (5.1%) | 39 (5.1%) | (0.0%) | 36 (3.7%) | 36 (3.7%) | (0.0%) | ||||||||||
| Infection/febrile neutropenia | ||||||||||||||||
| Febrile neutropenia* | 33 (4.3%) | 32 (4.2%) | 1 (0.1%) | 57 (5.9%) | 57 (5.9%) | (0.0%) | ||||||||||
| Infection* | 38 (5.0%) | 38 (5.0%) | (0.0%) | 71 (7.3%) | 70 (7.2%) | 1 (0.1%) | ||||||||||
| Metabolic/laboratory | ||||||||||||||||
| Hyperglycemia | 14 (1.8%) | 14 (1.8%) | (0.0%) | 9 (0.9%) | 9 (0.9%) | (0.0%) | ||||||||||
| Neurology | ||||||||||||||||
| Adverse Event Term a | AC - T (n = 766) | AC - T + H (n = 969) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Any Grade | Grades 3–4 | Grade 5 | Any Grade | Grades 3–4 | Grade 5 | ||||||||
| Neuropathy-motor* | 38 (5.0%) | 8 (1.0%) | (0.0%) | 42 (4.3%) | 13 (1.3%) | (0.0%) | |||||||
| Neuropathy-sensory* | 132 (17.2%) | 29 (3.8%) | (0.0%) | 174 (18.0%) | 46 (4.7%) | (0.0%) | |||||||
| Pain | |||||||||||||
| Arthralgia (joint pain)* | 75 (9.8%) | 10 (1.3%) | (0.0%) | 133 (13.7%) | 18 (1.9%) | (0.0%) | |||||||
| Chest pain | 5 (0.7%) | 1 (0.1%) | (0.0%) | 13 (1.3%) | 5 (0.5%) | (0.0%) | |||||||
| Myalgia (muscle pain)* | 62 (8.1%) | 10 (1.3%) | (0.0%) | 110 (11.4%) | 10 (1.0%) | (0.0%) | |||||||
| Pulmonary | |||||||||||||
| Dyspnea (shortness of breath) | 3 (0.4%) | 3 (0.4%) | (0.0%) | 29 (3.0%) | 24 (2.5%) | (0.0%) | |||||||
| Pneumonitis/Pulmonary infiltrates* | 8 (1.0%) | 7 (0.9%) | 1 (0.1%) | 10 (1.0%) | 9 (0.9%) | (0.0%) | |||||||
a NCIC CTC terminology A = doxorubicin; AE = adverse event; C = cyclophosphamide; H = trastuzumab; T = paclitaxel; WBC = white blood cell. Note: Only treatment-related Grade 4 and 5 hematologic toxicities, Grade 3–5 non-hematologic toxicities, Grade 1–5 cardiac toxicities, as well as Grade 2–5 arthralgia, myalgia, nail changes, neuropathy–motor, and neuropathy–sensory adverse events were collected during the treatment period. During the post-treatment follow-up period, only Grade 3–5 cardiac ischemia/infarction, thrombosis/embolism, pneumonitis/pulmonary infiltrates, and lymphatic events were collected. *Adverse event term is itemized on the Adverse Event CRF. | |||||||||||||
BCIRG-006
(adjuvant concurrent: use of trastuzumab in combination with docetaxel)
Adverse events according to the National Cancer Institute - Common Terminology Criteria NCI-CTC v 2.0 classification occurring at a frequency of ≥ 1% for study BCIRG-006 are summarized in Table 17. For adverse events that could not be classified according to the NCI-CTC, the Coding Symbols for Thesaurus of Adverse Reaction Terms (COSTART) coding dictionary was used (see Table 18).
Table 17 Adverse Events of Any Grade with Incidence ≥ 1% in Study BCIRG-006 (5 Year Follow Up) According to NCI-CTC v 2.0 Classification
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |
|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) |
| Allergy/immunology | ||||||
| Allergic reaction/ hypersensitivity (including drug fever) | 98 (9.4%) | 12 (1.2%) | 133 (12.3%) | 19 (1.8%) | 157 (14.9%) | 28 (2.7%) |
| Allergic rhinitis (including sneezing, nasal stuffiness, postnasal drip) | 83 (8.0%) | (0.0%) | 138 (12.8%) | (0.0%) | 97 (9.2%) | (0.0%) |
| Auditory/hearing | ||||||
| Earache (otalgia) | 32 (3.1%) | (0.0%) | 30 (2.8%) | (0.0%) | 17 (1.6%) | (0.0%) |
| Inner ear/hearing | 26 (2.5%) | 1 (0.1%) | 33 (3.1%) | (0.0%) | 34 (3.2%) | 1 (0.1%) |
| Blood/bone marrow | ||||||
| Neutrophils/granulocytes (ANC/AGC) | 23 (2.2%) | 21 (2.0%) | 34 (3.2%) | 24 (2.2%) | 20 (1.9%) | 19 (1.8%) |
| Cardiovascular (general) | ||||||
| Cardiac left ventricular function | 30 (2.9%) | 6 (0.6%) | 81 (7.5%) | 22 (2.0%) | 27 (2.6%) | 1 (0.1%) |
| Edema | 30 | (0.0%) | 37 | (0.0%) | 33 | 1 |
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) | ||||||
| (2.9%) | (3.4%) | (3.1%) | (0.1%) | |||||||||
| Hypertension | 37 (3.6%) | 12 (1.2%) | 52 (4.8%) | 23 (2.1%) | 61 (5.8%) | 33 (3.1%) | ||||||
| Hypotension | 20 (1.9%) | 1 (0.1%) | 31 (2.9%) | (0.0%) | 19 (1.8%) | 2 (0.2%) | ||||||
| Pericardial effusion/ pericarditis | 14 (1.3%) | (0.0%) | 19 (1.8%) | (0.0%) | 17 (1.6%) | 1 (0.1%) | ||||||
| Phlebitis (superficial) | 14 (1.3%) | (0.0%) | 22 (2.0%) | (0.0%) | 9 (0.9%) | (0.0%) | ||||||
| Thrombosis/embolism | 17 (1.6%) | 16 (1.5%) | 21 (1.9%) | 19 (1.8%) | 30 (2.8%) | 28 (2.7%) | ||||||
| Cardiovascular (arrhythmia) | ||||||||||||
| Palpitations | 73 (7.0%) | (0.0%) | 88 (8.2%) | (0.0%) | 96 (9.1%) | (0.0%) | ||||||
| Sinus tachycardia | 46 (4.4%) | 4 (0.4%) | 44 (4.1%) | 1 (0.1%) | 55 (5.2%) | (0.0%) | ||||||
| Supraventricular arrhythmias (SVT/atrial fibrillation/ flutter) | 11 (1.1%) | 5 (0.5%) | 8 (0.7%) | 4 (0.4%) | 10 (0.9%) | 5 (0.5%) | ||||||
| Constitutional symptoms | ||||||||||||
| Fatigue (lethargy, malaise, asthenia) | 858 (82.4%) | 70 (6.7%) | 905 (84.0%) | 80 (7.4%) | 879 (83.2%) | 76 (7.2%) | ||||||
| Fever (in the absence of neutropenia, where neutropenia is defined as AGC < 1.0 x 10⁹/l) | 144 (13.8%) | 2 (0.2%) | 170 (15.8%) | 5 (0.5%) | 115 (10.9%) | 6 (0.6%) | ||||||
| Rigors, chills | 53 (5.1%) | (0.0%) | 86 (8.0%) | (0.0%) | 75 (7.1%) | (0.0%) | ||||||
| Sweating (diaphoresis) | 68 (6.5%) | (0.0%) | 66 (6.1%) | (0.0%) | 72 (6.8%) | (0.0%) | ||||||
| Weight gain | 205 (19.7%) | 10 (1.0%) | 253 (23.5%) | 6 (0.6%) | 255 (24.1%) | 9 (0.9%) | ||||||
| Weight loss | 82 (7.9%) | 2 (0.2%) | 100 (9.3%) | 2 (0.2%) | 69 (6.5%) | 3 (0.3%) | ||||||
| Dermatology/skin | ||||||||||||
| Alopecia | 1025 (98.5%) | (0.0%) | 1060 (98.4%) | (0.0%) | 1016 (96.2%) | 2 (0.2%) | ||||||
| Bruising (in absence of grade 3 or 4 thrombocytopenia) | 17 (1.6%) | (0.0%) | 17 (1.6%) | (0.0%) | 25 (2.4%) | (0.0%) | ||||||
| Dry skin | 74 (7.1%) | (0.0%) | 96 (8.9%) | (0.0%) | 60 (5.7%) | (0.0%) | ||||||
| Flushing | 46 (4.4%) | (0.0%) | 56 (5.2%) | (0.0%) | 76 (7.2%) | (0.0%) | ||||||
| Hand-foot skin reaction | 85 (8.2%) | 20 (1.9%) | 77 (7.1%) | 15 (1.4%) | 30 (2.8%) | (0.0%) | ||||||
| Injection site reaction | 64 (6.1%) | 3 (0.3%) | 61 (5.7%) | 1 (0.1%) | 78 (7.4%) | 2 (0.2%) | ||||||
| Nail changes | 512 (49.2%) | (0.0%) | 472 (43.8%) | (0.0%) | 302 (28.6%) | (0.0%) | ||||||
| Pigmentation changes (e.g., vitiligo) | 65 (6.2%) | (0.0%) | 67 (6.2%) | (0.0%) | 48 (4.5%) | (0.0%) | ||||||
| Pruritus | 29 (2.8%) | (0.0%) | 34 (3.2%) | 1 (0.1%) | 51 (4.8%) | 1 (0.1%) | ||||||
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |
|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) |
| Radiation dermatitis | 187 (18.0%) | 5 (0.5%) | 192 (17.8%) | 9 (0.8%) | 242 (22.9%) | 8 (0.8%) |
| Rash/desquamation | 295 (28.3%) | 18 (1.7%) | 369 (34.3%) | 14 (1.3%) | 348 (33.0%) | 9 (0.9%) |
| Wound- infectious | 22 (2.1%) | 4 (0.4%) | 33 (3.1%) | 6 (0.6%) | 38 (3.6%) | 9 (0.9%) |
Wound Non-infectious | 6 (0.6%) | (0.0%) | 11 (1.0%) | (0.0%) | 17 (1.6%) | (0.0%) |
| Gastrointestinal | ||||||
| Anorexia | 222 (21.3%) | 6 (0.6%) | 224 (20.8%) | 5 (0.5%) | 238 (22.5%) | 6 (0.6%) |
| Constipation | 396 (38.0%) | 8 (0.8%) | 389 (36.1%) | 15 (1.4%) | 351 (33.2%) | 6 (0.6%) |
| Dehydration | 30 (2.9%) | 5 (0.5%) | 39 (3.6%) | 4 (0.4%) | 42 (4.0%) | 5 (0.5%) |
| Diarrhea patients without colostomy: | 447 (42.9%) | 32 (3.1%) | 548 (50.9%) | 60 (5.6%) | 660 (62.5%) | 57 (5.4%) |
| Dyspepsia/ heartburn | 205 (19.7%) | 5 (0.5%) | 262 (24.3%) | 3 (0.3%) | 254 (24.1%) | 5 (0.5%) |
| Dysphagia, esophagitis, odynophagia (painful swallowing) | 45 (4.3%) | 2 (0.2%) | 45 (4.2%) | (0.0%) | 37 (3.5%) | 1 (0.1%) |
| Flatulence | 19 (1.8%) | (0.0%) | 23 (2.1%) | (0.0%) | 20 (1.9%) | (0.0%) |
| Gastritis | 17 (1.6%) | (0.0%) | 35 (3.2%) | 1 (0.1%) | 22 (2.1%) | (0.0%) |
| Mouth dryness | 85 (8.2%) | (0.0%) | 54 (5.0%) | (0.0%) | 37 (3.5%) | (0.0%) |
| Mucositis | 22 (2.1%) | 1 (0.1%) | 26 (2.4%) | 2 (0.2%) | 21 (2.0%) | 1 (0.1%) |
| Nausea | 911 (87.5%) | 62 (6.0%) | 946 (87.8%) | 61 (5.7%) | 864 (81.8%) | 51 (4.8%) |
| Proctitis | 29 (2.8%) | (0.0%) | 34 (3.2%) | (0.0%) | 39 (3.7%) | (0.0%) |
| Salivary gland changes | 11 (1.1%) | (0.0%) | 9 (0.8%) | (0.0%) | 7 (0.7%) | (0.0%) |
| Sense of smell | 14 (1.3%) | (0.0%) | 18 (1.7%) | (0.0%) | 8 (0.8%) | (0.0%) |
| Stomatitis/pharyngitis (oral/pharyngeal mucositis) | 681 (65.4%) | 37 (3.6%) | 717 (66.6%) | 31 (2.9%) | 562 (53.2%) | 15 (1.4%) |
| Taste disturbance (dysgeusia) | 298 (28.6%) | (0.0%) | 304 (28.2%) | (0.0%) | 320 (30.3%) | (0.0%) |
| Vomiting | 577 (55.4%) | 65 (6.2%) | 616 (57.2%) | 72 (6.7%) | 434 (41.1%) | 37 (3.5%) |
| Hemorrhage | ||||||
| Epistaxis | 63 (6.1%) | (0.0%) | 140 (13.0%) | (0.0%) | 170 (16.1%) | 4 (0.4%) |
| Rectal bleeding/hematochezia | 23 (2.2%) | (0.0%) | 36 (3.3%) | 1 (0.1%) | 28 (2.7%) | 1 (0.1%) |
| Vaginal bleeding | 34 (3.3%) | 2 (0.2%) | 24 (2.2%) | 2 (0.2%) | 24 (2.3%) | 1 (0.1%) |
| Endocrine |
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |
|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) |
| Hot flashes/flushes | 356 (34.2%) | 1 (0.1%) | 379 (35.2%) | 2 (0.2%) | 349 (33.0%) | (0.0%) |
| Infection/febrile neutropenia | ||||||
| Catheter-related infection | 18 (1.7%) | 7 (0.7%) | 30 (2.8%) | 14 (1.3%) | 26 (2.5%) | 8 (0.8%) |
| Febrile neutropenia (fever of unknown origin without clinically or microbiologically documented infection) (ANC < 1.0 x 10⁹/l, fever 38.5°c) | 97 (9.3%) | 96 (9.2%) | 117 (10.9%) | 117 (10.9%) | 100 (9.5%) | 100 (9.5%) |
| Infection (documented clinically or microbiologically) with grade 3 or 4 neutropenia | 119 (11.4%) | 116 (11.1%) | 131 (12.2%) | 129 (12.0%) | 118 (11.2%) | 118 (11.2%) |
| Infection with unknown ANC | 122 (11.7%) | 120 (11.5%) | 120 (11.1%) | 117 (10.9%) | 87 (8.2%) | 86 (8.1%) |
| Infection without neutropenia | 241 (23.2%) | 33 (3.2%) | 326 (30.3%) | 50 (4.6%) | 248 (23.5%) | 37 (3.5%) |
| Lymphatics | ||||||
| Lymphatics | 68 (6.5%) | (0.0%) | 71 (6.6%) | 3 (0.3%) | 81 (7.7%) | 2 (0.2%) |
| Metabolic/laboratory | ||||||
| Hyperglycemia | 80 (7.7%) | 18 (1.7%) | 81 (7.5%) | 12 (1.1%) | 79 (7.5%) | 20 (1.9%) |
| Hypokalemia | 17 (1.6%) | 2 (0.2%) | 22 (2.0%) | 4 (0.4%) | 24 (2.3%) | 6 (0.6%) |
| Hypomagnesemia | 5 (0.5%) | (0.0%) | (0.0%) | (0.0%) | 12 (1.1%) | 1 (0.1%) |
| Musculoskeletal | ||||||
| Muscle weakness (not due to neuropathy) | 36 (3.5%) | 2 (0.2%) | 36 (3.3%) | 3 (0.3%) | 30 (2.8%) | (0.0%) |
| Neurology | ||||||
| Cognitive disturbance/ learning problems | 10 (1.0%) | (0.0%) | 8 (0.7%) | (0.0%) | 3 (0.3%) | (0.0%) |
| Confusion | 10 (1.0%) | (0.0%) | 9 (0.8%) | 2 (0.2%) | 6 (0.6%) | (0.0%) |
| Dizziness/lightheadedness | 113 (10.9%) | 6 (0.6%) | 151 (14.0%) | 7 (0.6%) | 129 (12.2%) | 4 (0.4%) |
| Insomnia | 234 (22.5%) | 1 (0.1%) | 278 (25.8%) | 5 (0.5%) | 252 (23.9%) | 3 (0.3%) |
| Memory loss | 37 (3.6%) | (0.0%) | 34 (3.2%) | 1 (0.1%) | 31 (2.9%) | 1 (0.1%) |
| Mood alteration- anxiety agitation | 133 (12.8%) | 8 (0.8%) | 126 (11.7%) | 5 (0.5%) | 101 (9.6%) | 4 (0.4%) |
| Mood alteration- depression | 108 (10.4%) | 4 (0.4%) | 135 (12.5%) | 13 (1.2%) | 122 (11.6%) | 6 (0.6%) |
| Neuropathy-motor | 55 (5.3%) | 4 (0.4%) | 68 (6.3%) | 8 (0.7%) | 45 (4.3%) | 3 (0.3%) |
| Neuropathy-sensory | 511 (49.1%) | 25 (2.4%) | 542 (50.3%) | 25 (2.3%) | 384 (36.4%) | 8 (0.8%) |
| Syncope (fainting) | 20 (1.9%) | 20 (1.9%) | 20 (1.9%) | 20 (1.9%) | 19 (1.8%) | 19 (1.8%) |
| Vertigo | 16 | (0.0%) | 37 | 3 | 28 | 6 |
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) | ||||||
| (1.5%) | (3.4%) | (0.3%) | (2.7%) | (0.6%) | ||||||||
| Pain | ||||||||||||
| Abdominal pain or cramping | 184 (17.7%) | 7 (0.7%) | 215 (20.0%) | 8 (0.7%) | 237 (22.4%) | 8 (0.8%) | ||||||
| Arthralgia (joint pain) | 436 (41.9%) | 34 (3.3%) | 497 (46.1%) | 35 (3.2%) | 313 (29.6%) | 15 (1.4%) | ||||||
| Bone pain | 188 (18.1%) | 17 (1.6%) | 224 (20.8%) | 10 (0.9%) | 141 (13.4%) | 3 (0.3%) | ||||||
| Chest pain (non-cardiac and non-pleuritic) | 59 (5.7%) | 1 (0.1%) | 79 (7.3%) | 7 (0.6%) | 72 (6.8%) | 3 (0.3%) | ||||||
| Headache | 307 (29.5%) | 11 (1.1%) | 316 (29.3%) | 16 (1.5%) | 304 (28.8%) | 7 (0.7%) | ||||||
| Myalgia (muscle pain) | 551 (52.9%) | 54 (5.2%) | 600 (55.7%) | 57 (5.3%) | 412 (39.0%) | 19 (1.8%) | ||||||
| Neuropathic pain (e.g., jaw pain, neurologic pain, phantom limb pain, post- infectious neuralgia, or painful neuropathies) | 18 (1.7%) | 1 (0.1%) | 16 (1.5%) | 2 (0.2%) | 10 (0.9%) | 1 (0.1%) | ||||||
| Pulmonary | ||||||||||||
| Cough | 189 (18.2%) | 3 (0.3%) | 204 (18.9%) | 3 (0.3%) | 143 (13.5%) | (0.0%) | ||||||
| Dyspnea (shortness of breath) | 229 (22.0%) | 12 (1.2%) | 264 (24.5%) | 30 (2.8%) | 227 (21.5%) | 23 (2.2%) | ||||||
| Voice changes/stridor/larynx (e.g., hoarseness, loss of voice, laryngitis) | 10 (1.0%) | 1 (0.1%) | 12 (1.1%) | 1 (0.1%) | 11 (1.0%) | 1 (0.1%) | ||||||
| Ocular/visual | ||||||||||||
| Conjunctivitis | 94 (9.0%) | 5 (0.5%) | 112 (10.4%) | 1 (0.1%) | 43 (4.1%) | (0.0%) | ||||||
| Dry eye | 44 (4.2%) | (0.0%) | 53 (4.9%) | (0.0%) | 30 (2.8%) | (0.0%) | ||||||
| Tearing (watery eyes) | 213 (20.5%) | (0.0%) | 258 (24.0%) | 3 (0.3%) | 124 (11.7%) | (0.0%) | ||||||
| Vision- blurred vision | 35 (3.4%) | (0.0%) | 51 (4.7%) | 2 (0.2%) | 55 (5.2%) | (0.0%) | ||||||
| Renal/genitourinary | ||||||||||||
| Dysuria (painful urination) | 25 (2.4%) | (0.0%) | 48 (4.5%) | (0.0%) | 56 (5.3%) | 1 (0.1%) | ||||||
| Incontinence | 3 (0.3%) | (0.0%) | 10 (0.9%) | 1 (0.1%) | 15 (1.4%) | (0.0%) | ||||||
| Urinary frequency/urgency | 26 (2.5%) | (0.0%) | 34 (3.2%) | (0.0%) | 25 (2.4%) | (0.0%) | ||||||
| Vaginitis (not due to infection) | 17 (1.6%) | (0.0%) | 16 (1.5%) | (0.0%) | 14 (1.3%) | 1 (0.1%) | ||||||
| Sexual/reproductive function | ||||||||||||
| Irregular menses (change from baseline) | 372 (35.7%) | 283 (27.2%) | 349 (32.4%) | 262 (24.3%) | 383 (36.3%) | 283 (26.8%) | ||||||
| Libido | 6 (0.6%) | (0.0%) | 9 (0.8%) | (0.0%) | 11 (1.0%) | (0.0%) | ||||||
| Vaginal dryness | 33 (3.2%) | (0.0%) | 44 (4.1%) | (0.0%) | 49 (4.6%) | (0.0%) | ||||||
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | ||||
|---|---|---|---|---|---|---|---|---|---|
| NCI-CTC term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) | |||
A=doxorubicin; C=cyclophosphamide; H=trastuzumab; T =docetaxel; C (in TCH)=carboplatin Note: In the BCIRG-006 study, all grade hematological and non-hematological AEs, and cardiac AEs were collected, as well as laboratory data. | |||||||||
Table 18 Adverse Events of Any Grade with Incidence ≥ 1% in Study BCIRG-006 (5 Year Follow Up) According to COSTART Classification
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |
|---|---|---|---|---|---|---|
| COSTART term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) |
| Body as a whole | ||||||
| Accidental injury | 19 (1.8%) | 2 (0.2%) | 18 (1.7%) | 1 (0.1%) | 20 (1.9%) | 3 (0.3%) |
| Back pain | 83 (8.0%) | 3 (0.3%) | 133 (12.3%) | 12 (1.1%) | 97 (9.2%) | 5 (0.5%) |
| Chest pain | 13 (1.2%) | 1 (0.1%) | 14 (1.3%) | (0.0%) | 10 (0.9%) | 1 (0.1%) |
| Cyst | 13 (1.2%) | 1 (0.1%) | 12 (1.1%) | 1 (0.1%) | 13 (1.2%) | 1 (0.1%) |
| Face edema | 12 (1.2%) | (0.0%) | 16 (1.5%) | (0.0%) | 12 (1.1%) | (0.0%) |
| Fever | 32 (3.1%) | 7 (0.7%) | 30 (2.8%) | 2 (0.2%) | 22 (2.1%) | 4 (0.4%) |
| Flu syndrome | 33 (3.2%) | (0.0%) | 33 (3.1%) | (0.0%) | 29 (2.7%) | (0.0%) |
| Injection site pain | 23 (2.2%) | (0.0%) | 39 (3.6%) | (0.0%) | 40 (3.8%) | 1 (0.1%) |
| Neck pain | 14 (1.3%) | 1 (0.1%) | 13 (1.2%) | (0.0%) | 16 (1.5%) | (0.0%) |
| Pain | 228 (21.9%) | 5 (0.5%) | 257 (23.9%) | 8 (0.7%) | 208 (19.7%) | 3 (0.3%) |
| Cardiac adverse events (body as a whole) | ||||||
| Chest pain | 7 (0.7%) | (0.0%) | 16 (1.5%) | (0.0%) | 16 (1.5%) | (0.0%) |
| Cardiac adverse events (cardiovascular system) | ||||||
| Cardiomegaly | 7 (0.7%) | (0.0%) | 18 (1.7%) | (0.0%) | 9 (0.9%) | (0.0%) |
| Cardiovascular disorder | 16 (1.5%) | 1 (0.1%) | 25 (2.3%) | (0.0%) | 16 (1.5%) | 1 (0.1%) |
| Hemorrhage | 19 (1.8%) | (0.0%) | 11 (1.0%) | 2 (0.2%) | 9 (0.9%) | 2 (0.2%) |
| Tachycardia | 7 (0.7%) | (0.0%) | 18 (1.7%) | (0.0%) | 14 (1.3%) | 2 (0.2%) |
| Digestive system | ||||||
| Anorexia | 14 (1.3%) | (0.0%) | 12 (1.1%) | (0.0%) | 16 (1.5%) | (0.0%) |
| Dyspepsia | 7 (0.7%) | (0.0%) | 10 (0.9%) | (0.0%) | 17 (1.6%) | (0.0%) |
| Esophagitis | 20 (1.9%) | 2 (0.2%) | 8 (0.7%) | (0.0%) | 12 (1.1%) | (0.0%) |
| Flatulence | 16 (1.5%) | (0.0%) | 24 (2.2%) | (0.0%) | 22 (2.1%) | (0.0%) |
| Gum hemorrhage | 1 (0.1%) | (0.0%) | 14 (1.3%) | (0.0%) | 5 (0.5%) | (0.0%) |
| Rectal disorder | 17 (1.6%) | (0.0%) | 23 (2.1%) | 1 (0.1%) | 28 (2.7%) | 2 (0.2%) |
| Hemic and lymphatic system | ||||||
| Lymphedema | 21 (2.0%) | (0.0%) | 23 (2.1%) | 1 (0.1%) | 28 (2.7%) | (0.0%) |
| Metabolic and nutritional disorders | ||||||
| Edema | 4 (0.4%) | (0.0%) | 6 (0.6%) | (0.0%) | 13 (1.2%) | (0.0%) |
| Peripheral edema | 349 (33.5%) | 4 (0.4%) | 395 (36.7%) | 4 (0.4%) | 346 (32.8%) | 2 (0.2%) |
| Musculoskeletal system | ||||||
| Arthralgia | 19 (1.8%) | (0.0%) | 20 (1.9%) | (0.0%) | 24 (2.3%) | 1 (0.1%) |
| Joint disorder | 9 (0.9%) | (0.0%) | 7 (0.6%) | 1 (0.1%) | 10 (0.9%) | 1 (0.1%) |
| Osteoporosis | 6 (0.6%) | (0.0%) | 11 (1.0%) | 1 (0.1%) | 12 (1.1%) | 1 (0.1%) |
| Nervous system | ||||||
| Hypertonia | 6 (0.6%) | (0.0%) | 11 (1.0%) | (0.0%) | 16 (1.5%) | (0.0%) |
| Leg cramps | 8 (0.8%) | (0.0%) | 13 (1.2%) | (0.0%) | 7 (0.7%) | (0.0%) |
| Neuropathy | 8 (0.8%) | 1 (0.1%) | 10 (0.9%) | (0.0%) | 9 (0.9%) | 2 (0.2%) |
| Twitching | 7 (0.7%) | (0.0%) | 13 (1.2%) | (0.0%) | 26 (2.5%) | (0.0%) |
| Respiratory system |
Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |
|---|---|---|---|---|---|---|
| COSTART term | AC->T (n=1041) | AC->T (n=1041) | AC->TH (n=1077) | AC->TH (n=1077) | TCH (n=1056) | TCH (n=1056) |
| Pharyngitis | 71 (6.8%) | (0.0%) | 83 (7.7%) | (0.0%) | 55 (5.2%) | 2 (0.2%) |
| Rhinitis | 111 (10.7%) | 1 (0.1%) | 142 (13.2%) | 1 (0.1%) | 108 (10.2%) | (0.0%) |
| Sinusitis | 18 (1.7%) | (0.0%) | 21 (1.9%) | 1 (0.1%) | 22 (2.1%) | 1 (0.1%) |
| Skin and appendages | ||||||
| Acne | 11 (1.1%) | (0.0%) | 28 (2.6%) | (0.0%) | 33 (3.1%) | (0.0%) |
| Herpes simplex | 20 (1.9%) | 1 (0.1%) | 27 (2.5%) | 4 (0.4%) | 19 (1.8%) | 1 (0.1%) |
| Nail disorder | 11 (1.1%) | (0.0%) | 5 (0.5%) | (0.0%) | 3 (0.3%) | (0.0%) |
| Pruritus | 10 (1.0%) | (0.0%) | 16 (1.5%) | 1 (0.1%) | 16 (1.5%) | (0.0%) |
| Skin and appendages | ||||||
| Rash | 38 (3.7%) | 1 (0.1%) | 55 (5.1%) | (0.0%) | 42 (4.0%) | 1 (0.1%) |
| Skin disorder | 6 (0.6%) | (0.0%) | 13 (1.2%) | (0.0%) | 11 (1.0%) | (0.0%) |
| Special senses | ||||||
| Abnormal vision | 9 (0.9%) | (0.0%) | 14 (1.3%) | (0.0%) | 13 (1.2%) | (0.0%) |
| Conjunctivitis | 17 (1.6%) | (0.0%) | 10 (0.9%) | (0.0%) | 2 (0.2%) | (0.0%) |
| Eye pain | 16 (1.5%) | (0.0%) | 15 (1.4%) | (0.0%) | 16 (1.5%) | (0.0%) |
| Urogenital system | ||||||
| Breast pain | 53 (5.1%) | (0.0%) | 57 (5.3%) | 1 (0.1%) | 61 (5.8%) | 2 (0.2%) |
| Leukorrhea | 16 (1.5%) | (0.0%) | 26 (2.4%) | (0.0%) | 19 (1.8%) | (0.0%) |
The toxicity profile of trastuzumab in all four adjuvant trials appears to be similar. Cardiac dysfunction is the main concern with trastuzumab treatment (see WARNINGS AND PRECAUTIONS).
Metastatic Breast Cancer (MBC)
In clinical trials conducted prior to marketing, a total of 958 patients received trastuzumab alone or in combination with chemotherapy. Data in
Table 20 are based on the experience with the recommended dosing regimen for trastuzumab in the randomized controlled clinical trial in 234 patients who received trastuzumab in combination with chemotherapy and the open-label study of trastuzumab as a single agent in 213 patients with HER2-overexpressing MBC.
Table 19 Adverse Events Occurring in ≥ 1% of Patients in Study H0649g (up to First Disease Progression on Study)
| Adverse event term | Single Agent (n=213) |
|---|---|
| Body as a whole | |
| Abdomen enlarged | 3 (1.4%) |
| Abdominal pain | 47 (22.1%) |
| Accidental injury | 12 (5.6%) |
| Allergic reaction | 4 (1.9%) |
| Ascites | 9 (4.2%) |
| Asthenia | 100 (46.9%) |
| Back pain | 44 (20.7%) |
| Carcinoma | 9 (4.2%) |
| Cellulitis | 3 (1.4%) |
| Chest pain | 46 (21.6%) |
| Chills | 76 (35.7%) |
| Chills and fever | 7 (3.3%) |
| Face edema | 4 (1.9%) |
| Fever | 83 (39.0%) |
| Adverse event term | Single Agent (n=213) |
|---|---|
| Flu syndrome | 24 (11.3%) |
| Headache | 56 (26.3%) |
| Infection | 42 (19.7%) |
| Injection site inflammation | 3 (1.4%) |
| Injection site pain | 4 (1.9%) |
| Malaise | 7 (3.3%) |
| Moniliasis | 4 (1.9%) |
| Mucous membrane disorder | 4 (1.9%) |
| Neck pain | 11 (5.2%) |
| Neoplasm | 4 (1.9%) |
| Pain | 105 (49.3%) |
| Pelvic pain | 8 (3.8%) |
| Procedure | 4 (1.9%) |
| Sepsis | 3 (1.4%) |
| Cardiovascular | |
| Cardiovascular disorder | 3 (1.4%) |
| Congestive heart failure | 4 (1.9%) |
| Heart arrest | 3 (1.4%) |
| Hemorrhage | 3 (1.4%) |
| Hypertension | 4 (1.9%) |
| Hypotension | 5 (2.3%) |
| Migraine | 4 (1.9%) |
| Palpitation | 4 (1.9%) |
| Tachycardia | 13 (6.1%) |
| Vascular disorder | 8 (3.8%) |
| Vasodilatation | 16 (7.5%) |
| Digestive | |
| Anorexia | 28 (13.1%) |
| Constipation | 27 (12.7%) |
| Diarrhea | 57 (26.8%) |
| Dry mouth | 6 (2.8%) |
| Dyspepsia | 17 (8.0%) |
| Dysphagia | 5 (2.3%) |
| Flatulence | 10 (4.7%) |
| Gastroenteritis | 3 (1.4%) |
| Gastrointestinal disorder | 4 (1.9%) |
| Hepatic failure | 4 (1.9%) |
| Jaundice | 6 (2.8%) |
| Liver tenderness | 7 (3.3%) |
| Mouth ulceration | 4 (1.9%) |
| Nausea | 79 (37.1%) |
| Nausea and vomiting | 16 (7.5%) |
| Oral moniliasis | 4 (1.9%) |
| Rectal disorder | 4 (1.9%) |
| Stomatitis | 9 (4.2%) |
| Vomiting | 60 (28.2%) |
| Hemic and lymphatic | |
| Anemia | 9 (4.2%) |
| Ecchymosis | 7 (3.3%) |
| Hypochromic anemia | 3 (1.4%) |
| Leukopenia | 7 (3.3%) |
| Lymphadenopathy | 3 (1.4%) |
| Lymphedema | 4 (1.9%) |
| Metabolic and nutritional disorders | |
| Dehydration | 5 (2.3%) |
| Adverse event term | Single Agent (n=213) |
|---|---|
| Edema | 17 (8.0%) |
| Hypercalcemia | 3 (1.4%) |
| Hypokalemia | 8 (3.8%) |
| Hypomagnesemia | 3 (1.4%) |
| Peripheral edema | 21 (9.9%) |
| Serum glutamic pyruvic transaminase (SGPT) increased | 3 (1.4%) |
| Weight gain | 4 (1.9%) |
| Weight loss | 7 (3.3%) |
| Musculoskeletal | |
| Arthralgia | 13 (6.1%) |
| Bone pain | 18 (8.5%) |
| Joint disorder | 3 (1.4%) |
| Leg cramps | 14 (6.6%) |
| Myalgia | 16 (7.5%) |
| Myasthenia | 6 (2.8%) |
| Nervous | |
| Abnormal gait | 5 (2.3%) |
| Amnesia | 3 (1.4%) |
| Anxiety | 28 (13.1%) |
| Circumoral paresthesia | 3 (1.4%) |
| Confusion | 4 (1.9%) |
| Convulsion | 4 (1.9%) |
| Depression | 16 (7.5%) |
| Dizziness | 28 (13.1%) |
| Hypertonia | 9 (4.2%) |
| Insomnia | 35 (16.4%) |
| Nervousness | 6 (2.8%) |
| Neuropathy | 4 (1.9%) |
| Paralysis | 3 (1.4%) |
| Paresthesia | 19 (8.9%) |
| Peripheral neuritis | 4 (1.9%) |
| Somnolence | 15 (7.0%) |
| Speech disorder | 3 (1.4%) |
| Thinking abnormal | 3 (1.4%) |
| Tremor | 4 (1.9%) |
| Vertigo | 3 (1.4%) |
| Respiratory | |
| Asthma | 13 (6.1%) |
| Bronchitis | 7 (3.3%) |
| Cough increased | 60 (28.2%) |
| Dyspnea | 49 (23.0%) |
| Epistaxis | 12 (5.6%) |
| Laryngitis | 3 (1.4%) |
| Lung disorder | 17 (8.0%) |
| Pharyngitis | 28 (13.1%) |
| Pleural effusion | 19 (8.9%) |
| Pneumonia | 3 (1.4%) |
| Pneumothorax | 4 (1.9%) |
| Rhinitis | 33 (15.5%) |
| Sinusitis | 25 (11.7%) |
| Voice alteration | 6 (2.8%) |
| Skin and appendages | |
| Acne | 4 (1.9%) |
| Alopecia | 3 (1.4%) |
| Dry skin | 4 (1.9%) |
| Adverse event term | Single Agent (n=213) |
|---|---|
| Herpes simplex | 5 (2.3%) |
| Herpes zoster | 4 (1.9%) |
| Nail disorder | 4 (1.9%) |
| Pruritus | 24 (11.3%) |
| Rash | 30 (14.1%) |
| Skin benign neoplasm | 3 (1.4%) |
| Skin ulcer | 3 (1.4%) |
| Sweating | 8 (3.8%) |
| Urticarial | 4 (1.9%) |
| Special senses | |
| Abnormal vision | 3 (1.4%) |
| Amblyopia | 9 (4.2%) |
| Conjunctivitis | 5 (2.3%) |
| Diplopia | 4 (1.9%) |
| Ear disorder | 5 (2.3%) |
| Ear pain | 5 (2.3%) |
| Taste perversion | 5 (2.3%) |
| Urogenital | |
| Breast carcinoma | 11 (5.2%) |
| Breast pain | 15 (7.0%) |
| Dysuria | 8 (3.8%) |
| Hematuria | 3 (1.4%) |
| Urinary frequency | 7 (3.3%) |
| Urinary tract infection | 7 (3.3%) |
| Vaginitis | 4 (1.9%) |
Table 20 Adverse Events Occurring in ≥ 1% of Patients in Study H0648g (up to First Disease Progression on Study)
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Body as a whole | ||||
| Abdomen enlarged | 2 (1.4%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Abdominal pain | 33 (23.1%) | 25 (18.5%) | 31 (34.1%) | 21 (22.1%) |
| Abscess | 2 (1.4%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Accidental injury | 13 (9.1%) | 6 (4.4%) | 12 (13.2%) | 3 (3.2%) |
| Allergic reaction | 6 (4.2%) | 3 (2.2%) | 7 (7.7%) | 2 (2.1%) |
| Anaphylactoid reaction | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Ascites | 3 (2.1%) | 6 (4.4%) | (0.0%) | 3 (3.2%) |
| Asthenia | 78 (54.5%) | 74 (54.8%) | 56 (61.5%) | 54 (56.8%) |
| Back pain | 39 (27.3%) | 21 (15.6%) | 33 (36.3%) | 29 (30.5%) |
| Carcinoma | 6 (4.2%) | 12 (8.9%) | 7 (7.7%) | 6 (6.3%) |
| Cellulitis | 2 (1.4%) | 3 (2.2%) | 3 (3.3%) | 5 (5.3%) |
| Chest pain | 29 (20.3%) | 28 (20.7%) | 27 (29.7%) | 26 (27.4%) |
| Chest pain substernal | 3 (2.1%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Chills | 50 (35.0%) | 15 (11.1%) | 38 (41.8%) | 4 (4.2%) |
| Chills and fever | 3 (2.1%) | 1 (0.7%) | 5 (5.5%) | 4 (4.2%) |
| Cyst | 2 (1.4%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Face edema | 2 (1.4%) | (0.0%) | 4 (4.4%) | 6 (6.3%) |
| Facial pain | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Fever | 80 (55.9%) | 45 (33.3%) | 43 (47.3%) | 22 (23.2%) |
| Flu syndrome | 17 (11.9%) | 8 (5.9%) | 11 (12.1%) | 5 (5.3%) |
| Headache | 63 (44.1%) | 42 (31.1%) | 33 (36.3%) | 27 (28.4%) |
| Hydrocephalus | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Hypothermia | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Immune system disorder | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Infection | 67 (46.9%) | 41 (30.4%) | 42 (46.2%) | 26 (27.4%) |
| Infection site edema | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Injection site hemorrhage | 1 (0.7%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Injection site hypersensitivity | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Injection site inflammation | 12 (8.4%) | 3 (2.2%) | 3 (3.3%) | 2 (2.1%) |
| Injection site pain | 8 (5.6%) | 4 (3.0%) | 4 (4.4%) | 5 (5.3%) |
| Injection site reaction | 6 (4.2%) | 1 (0.7%) | 6 (6.6%) | 1 (1.1%) |
| Lab test abnormal | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Le syndrome | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Malaise | 4 (2.8%) | 7 (5.2%) | 3 (3.3%) | 4 (4.2%) |
| Moniliasis | 3 (2.1%) | 3 (2.2%) | 1 (1.1%) | 1 (1.1%) |
| Mucous membrane disorder | 31 (21.7%) | 25 (18.5%) | 10 (11.0%) | 7 (7.4%) |
| Neck pain | 15 (10.5%) | 11 (8.1%) | 8 (8.8%) | 5 (5.3%) |
| Neck rigidity | 3 (2.1%) | (0.0%) | (0.0%) | 3 (3.2%) |
| Necrosis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Neoplasm | 5 (3.5%) | 3 (2.2%) | 3 (3.3%) | 1 (1.1%) |
| Pain | 82 (57.3%) | 56 (41.5%) | 55 (60.4%) | 58 (61.1%) |
| Pelvic pain | 1 (0.7%) | 2 (1.5%) | 4 (4.4%) | 2 (2.1%) |
| Photosensitivity reaction | 2 (1.4%) | (0.0%) | (0.0%) | (0.0%) |
| Procedure | 11 (7.7%) | 5 (3.7%) | 5 (5.5%) | 2 (2.1%) |
| Radiation injury | (0.0%) | 2 (1.5%) | 1 (1.1%) | 2 (2.1%) |
| Reaction unevaluable | 14 (9.8%) | 9 (6.7%) | 4 (4.4%) | 2 (2.1%) |
| Sepsis | 10 (7.0%) | 9 (6.7%) | 4 (4.4%) | 1 (1.1%) |
| Sudden death | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Angina pectoris | 3 (2.14%) | (0.0%) | (0.0%) | (0.0%) |
| Arrhythmia | 1 (0.7%) | 2 (1.5%) | (0.0%) | 2 (2.1%) |
| Atrial fibrillation | (0.0%) | 1 (0.7%) | 1 (1.1%) | 2 (2.1%) |
| Atrial flutter | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Bradycardia | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Cardiomegaly | 2 (1.4%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Cardiomyopathy | 10 (7.0%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Cardiovascular disorder | 3 (2.1%) | 7 (5.2%) | 3 (3.3%) | 1 (1.1%) |
| Cerebrovascular accident | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Congestive heart failure | 17 (11.9%) | 2 (1.5%) | 2 (2.2%) | 1 (1.1%) |
| Deep thrombophlebitis | 4 (2.8%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Electrocardiogram abnormal | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Endocarditis | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Heart arrest | (0.0%) | 1 (0.7%) | 1 (1.1%) | 2 (2.1%) |
| Heart failure | 1(0.7%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Hemorrhage | 2 (1.4%) | 1 (0.7%) | 3 (3.3%) | (0.0%) |
| Hypertension | 5 (3.5%) | 4 (3.0%) | 5 (5.5%) | 4 (4.2%) |
| Hypotension | 10 (7.0%) | 5 (3.7%) | 2 (2.2%) | 3 (3.2%) |
| Left heart failure | 14 (9.8%) | 7 (5.2%) | 5 (5.5%) | (0.0%) |
| Migraine | (0.0%) | 2 (1.5%) | 1 (1.1%) | 3 (3.2%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Myocardial ischemia | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Pallor | 7 (4.9%) | 2 (1.5%) | 1 (1.1%) | 2 (2.1%) |
| Palpitation | 8 (5.6%) | 5 (3.7%) | 4 (4.4%) | 2 (2.1%) |
| Pericardial effusion | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Peripheral vascular disorder | (0.0%) | (0.0%) | 2 (2.2%) | 3 (3.2%) |
| Phlebitis | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Postural hypotension | 4 (2.8%) | 2 (1.5%) | 1 (1.1%) | 1 (1.1%) |
| Pulmonary embolus | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Shock | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Sinus bradycardia | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Syncope | 4 (2.8%) | 3 (2.2%) | 4 (4.4%) | 3 (3.2%) |
| Tachycardia | 14 (9.8%) | 7 (5.2%) | 11 (12.1%) | 4 (4.2%) |
| Thrombophlebitis | 2 (1.4%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Thrombosis | 3 (2.1%) | (0.0%) | 2 (2.2%) | (0.0%) |
| Varicose vein | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Vascular disorder | 9 (6.3%) | 7 (5.2%) | 2 (2.2%) | 2 (2.1%) |
| Vasodilatation | 25 (17.5%) | 22 (16.3%) | 20 (22.0%) | 19 (20.0%) |
| Ventricular fibrillation | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Ventricular tachycardia | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Digestive | ||||
| Abnormal stools | 2 (1.4%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Anorexia | 44 (30.8%) | 35 (25.9%) | 22 (24.2%) | 15 (15.8%) |
| Cheilitis | 1 (0.7%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Cholelithiasis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Cirrhosis of liver | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Colitis | 3 (2.1%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Constipation | 51 (35.7%) | 38 (28.1%) | 23 (25.3%) | 26 (27.4%) |
| Diarrhea | 64 (44.8%) | 34 (25.2%) | 41 (45.1%) | 28 (29.5%) |
| Dry mouth | 9 (6.3%) | 12 (8.9%) | 7 (7.7%) | 5 (5.3%) |
| Dyspepsia | 32 (22.4%) | 27 (20.0%) | 16 (17.6%) | 15 (15.8%) |
| Dysphagia | 11 (7.7%) | 5 (3.7%) | 3 (3.3%) | 2 (2.1%) |
| Eructation | 2 (1.4%) | (0.0%) | (0.0%) | (0.0%) |
| Esophageal stenosis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Esophageal ulcer | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Esophagitis | 2 (1.4%) | 8 (5.9%) | (0.0%) | 2 (2.1%) |
| Fecal impaction | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Fecal incontinence | (0.0%) | 1 (0.7%) | 3 (3.3%) | (0.0%) |
| Flatulence | 5 (3.5%) | 8 (5.9%) | 1 (1.1%) | 5 (5.3%) |
| Gastritis | 3 (2.1%) | 4 (3.0%) | 3 (3.3%) | (0.0%) |
| Gastroenteritis | 2 (1.4%) | 5 (3.7%) | 2 (2.2%) | (0.0%) |
| Gastrointestinal carcinoma | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Gastrointestinal disorder | 7 (4.9%) | 5 (3.7%) | 5 (5.5%) | 2 (2.1%) |
| Gastrointestinal hemorrhage | 3 (2.1%) | 2 (1.5%) | 2 (2.2%) | 2 (2.1%) |
| Gingivitis | 4 (2.8%) | 2 (1.5%) | 2 (2.2%) | (0.0%) |
| Glossitis | 3 (2.1%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Gum hemorrhage | 3 (2.1%) | (0.0%) | (0.0%) | (0.0%) |
| Hematemesis | 1 (0.7%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Hepatic failure | (0.0%) | 1 (0.7%) | 1 (1.1%) | 3 (3.2%) |
| Hepatic neoplasia | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Hepatitis | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Hepatomegaly | 2 (1.4%) | 1 (0.7%) | 3 (3.3%) | 1 (1.1%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Hepatosplenomegaly | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Ileus | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Increased appetite | (0.0%) | (0.0%) | 2 (2.2%) | 1 (1.1%) |
| Increased salivation | 3 (2.1%) | (0.0%) | (0.0%) | (0.0%) |
| Intestinal obstruction | (0.0%) | 1 (0.7%) | (0.0%) | 1 (1.1%) |
| Jaundice | (0.0%) | 1 (0.7%) | 1 (1.1%) | 4 (4.2%) |
| Liver damage | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Liver function tests abnormal | 2 (1.4%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Liver tenderness | 1 (0.7%) | 2 (1.5%) | 2 (2.2%) | 1 (1.1%) |
| Melena | (0.0%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Mouth ulceration | 17 (11.9%) | 19 (14.1%) | 4 (4.4%) | 1 (1.1%) |
| Nausea | 109 (76.2%) | 107 (79.3%) | 46 (50.5%) | 46 (48.4%) |
| Nausea and vomiting | 26 (18.2%) | 12 (8.9%) | 13 (14.3%) | 11 (11.6%) |
| Oral moniliasis | 5 (3.5%) | 6 (4.4%) | 4 (4.4%) | 6 (6.3%) |
| Periodontal abscess | 1 (0.7%) | (0.0%) | 3 (3.3%) | (0.0%) |
| Pseudomembranous colitis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Rectal disorder | 10 (7.0%) | 8 (5.9%) | 6 (6.6%) | (0.0%) |
| Rectal hemorrhage | 6 (4.2%) | 1 (0.7%) | 4 (4.4%) | 1 (1.1%) |
| Stomach ulcer | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Stomatitis | 43 (30.1%) | 42 (31.1%) | 9 (9.9%) | 7 (7.4%) |
| Tenesmus | 4 (2.8%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Thirst | 3 (2.1%) | 1 (0.7%) | (0.0%) | 1 (1.1%) |
| Tongue discoloration | 1 (0.7%) | (0.0%) | (0.0%) | (0.0% |
| Tongue disorder | 2 (1.4%) | 7 (5.2%) | 1 (1.1%) | (0.0%) |
| Tooth discoloration | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Tooth disorder | 2 (1.4%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Ulcerative stomatitis | 1 (0.7%) | 2 (1.5%) | (0.0%) | 2 (2.1%) |
| Vomiting | 76 (53.1%) | 66 (48.9%) | 34 (37.4%) | 27 (28.4%) |
| Endocrine | ||||
| Cushings syndrome | 1 (0.7%) | 4 (3.0%) | (0.0%) | 1 (1.1%) |
| Diabetes mellitus | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Goiter | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Hyperthyroidism | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Hypothyroidism | 3 (2.1%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Thyroiditis | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Hemic and lymphatic | ||||
| Acute leukemia | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Anemia | 50 (35.0%) | 34 (25.2%) | 13 (14.3%) | 9 (9.5%) |
| Bleeding time increased | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Coagulation disorder | (0.0%) | (0.0%) | 1 (1.1%) | 1 (1.1%) |
| Ecchymosis | 9 (6.3%) | 3 (2.2%) | 7 (7.7%) | 2 (2.1%) |
| Hemolytic anemia | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Hypochromic anemia | 8 (5.6%) | 1 (0.7%) | 2 (2.2%) | 2 (2.1%) |
| Leukocytosis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Leukopenia | 74 (51.7%) | 45 (33.3%) | 22 (24.2%) | 16 (16.8%) |
| Lymphadenopathy | 6 (4.2%) | 4 (3.0%) | 2 (2.2%) | 1 (1.1%) |
| Lymphangitis | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Lymphedema | 8 (5.6%) | 4 (3.0%) | 3 (3.3%) | 1 (1.1%) |
| Marrow depression | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Myeloid maturation arrest | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Pancytopenia | 5 (3.5%) | 3 (2.2%) | 2 (2.2%) | 1 (1.1%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Petechia | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Purpura | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Thrombocythemia | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Thrombocytopenia | 16 (11.2%) | 12 (8.9%) | 3 (3.3%) | 3 (3.2%) |
| Thromboplastin increased | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Metabolic and nutritional disorders | ||||
| Acidosis | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Alkaline phosphatase increased | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Bilirubinemia | (0.0%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Cachexia | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Creatinine increased | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Dehydration | 15 (10.5%) | 5 (3.7%) | 8 (8.8%) | 9 (9.5%) |
| Edema | 16 (11.2%) | 7 (5.2%) | 9 (9.9%) | 8 (8.4%) |
| Electrolyte abnormality | (0.0%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Glucose tolerance decreased | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Gout | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Growth retarded | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Healing abnormal | 4 (2.8%) | (0.0%) | 1 (1.1%) | 2 (2.1%) |
| Hypercalcemia | (0.0%) | 1 (0.7%) | 3 (3.3%) | 6 (6.3%) |
| Hypercholesteremia | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Hyperglycemia | 2 (1.4%) | 4 (3.0%) | 2 (2.2%) | 2 (2.14%) |
| Hyperkalemia | (0.0%) | (0.0%) | 3 (3.3%) | 2 (2.1%) |
| Hypernatremia | (0.0%) | (0.0%) | 1 (1.1%) | 1 (1.1%) |
| Hyperuricemia | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Hypervolemia | (0.0%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Hypocalcemia | 2 (1.4%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Hypoglycemia | 1 (0.7%) | 1 (0.7%) | (0.0%) | 3 (3.2%) |
| Hypokalemia | 18 (12.6%) | 6 (4.4%) | 2 (2.2%) | 3 (3.2%) |
| Hypomagnesemia | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Hyponatremia | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Hypophosphatemia | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Hypoproteinemia | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Lactic dehydrogenase increased | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| NPN increased | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Peripheral edema | 29 (20.3%) | 23 (17.0%) | 20 (22.0%) | 19 (20.0%) |
| SGOT (serum glutamic oxaloacetic transaminase) increased | (0.0%) | 1 (0.7%) | 2 (2.2%) | 3 (3.2%) |
| serum glutamic pyruvic transaminase (SGPT) increased | (0.0%) | (0.0%) | 2 (2.2%) | 1 (1.1%) |
| Weight gain | 4 (2.8%) | 3 (2.2%) | 2 (2.2%) | 2 (2.1%) |
| Weight loss | 12 (8.4%) | 8 (5.9%) | 7 (7.7%) | 5 (5.3%) |
| Musculoskeletal | ||||
| Arthralgia | 12 (8.4%) | 13 (9.6%) | 34 (37.4%) | 20 (21.1%) |
| Arthritis | 3 (2.1%) | (0.0%) | 4 (4.4%) | 1 (1.1%) |
| Bone disorder | (0.0%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Bone necrosis | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Bone pain | 10 (7.0%) | 9 (6.7%) | 22 (24.2%) | 17 (17.9%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Joint disorder | 5 (3.5%) | 2 (1.5%) | 2 (2.2%) | 3 (3.2%) |
| Leg cramps | 6 (4.2%) | 3 (2.2%) | 5 (5.5%) | 2 (2.1%) |
| Myalgia | 19 (13.3%) | 17 (12.6%) | 35 (38.5%) | 34 (35.8%) |
| Myasthenia | 4 (2.8%) | 8 (5.9%) | 6 (6.6%) | 8 (8.4%) |
| Myopathy | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Myositis | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Osteoporosis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Pathological fracture | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Rheumatoid arthritis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Tendinous contracture | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Tenosynovitis | (0.0%) | (0.0%) | 2 (2.2%) | (0.0%) |
| Twitching | 1 (0.7%) | 1 (0.7%) | (0.0%) | 2 (2.1%) |
| Nervous | ||||
| Abnormal dreams | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Abnormal gait | 3 (2.1%) | 4 (3.0%) | 7 (7.7%) | 4 (4.2%) |
| Agitation | 2 (1.4%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Amnesia | 3 (2.1%) | 4 (3.0%) | 2 (2.2%) | 1 (1.1%) |
| Anxiety | 26 (18.2%) | 19 (14.1%) | 17 (18.7%) | 14 (14.7%) |
| Ataxia | 2 (1.4%) | 3 (2.2%) | 6 (6.6%) | 4 (4.2%) |
| Brain edema | 2 (1.4%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Circumoral paresthesia | 1 (0.7%) | 1 (0.7%) | 2 (2.2%) | 1 (1.1%) |
| Coma | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Confusion | 8 (5.6%) | (0.0%) | 3 (3.3%) | 6 (6.3%) |
| Convulsion | 1 (0.7%) | (0.0%) | 2 (2.2%) | 3 (3.2%) |
| Depression | 28 (19.6%) | 16 (11.9%) | 11 (12.1%) | 12 (12.6%) |
| Dizziness | 34 (23.8%) | 24 (17.8%) | 20 (22.0%) | 23 (24.2%) |
| Dystonia | 2 (1.4%) | (0.0%) | (0.0%) | (0.0%) |
| Emotional lability | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Euphoria | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Extraphyramidal syndrome | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Foot drop | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Guillain barre syndrome | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Hallucinations | 2 (1.4%) | (0.0%) | 1 (1.1%) | 2 (2.1%) |
| Hyperesthesia | 3 (2.1%) | (0.0%) | 2 (2.2%) | 3 (3.2%) |
| Hyperkinesia | 2 (1.4%) | (0.0%) | 3 (3.3%) | 2 (2.1%) |
| Hypertonia | 11 (7.7%) | 3 (2.2%) | 10 (11.0%) | 3 (3.2%) |
| Hypesthesia | 1 (0.7%) | 1 (0.7%) | 1 (1.1%) | 3 (3.2%) |
| Hypokinesia | (0.0%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Incoordination | 2 (1.4%) | (0.0%) | 1 (1.1%) | 3 (3.2%) |
| Insomnia | 42 (29.4%) | 21 (15.6%) | 23 (25.3%) | 12 (12.6%) |
| Meningitis | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Movement disorder | (0.0%) | 3 (2.2%) | 1 (1.1%) | 1 (1.1%) |
| Nervousness | 6 (4.2%) | 5 (3.7%) | 4 (4.4%) | 2 (2.1%) |
| Neuralgia | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | 2 (2.1%) |
| Neuropathy | 5 (3.5%) | 6 (4.4%) | 12 (13.2%) | 5 (5.3%) |
| Neurosis | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Nystagmus | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Paranoid reaction | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Paraplegia | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Parasthesia | 24 (16.8%) | 15 (11.1%) | 43 (47.3%) | 37 (38.9%) |
| Peripheral neuritis | 3 (2.1%) | 3 (2.2%) | 21 (23.1%) | 15 (15.8%) |
| Reflexes decreased | (0.0%) | 1 (0.7%) | 3 (3.3%) | 1 (1.1%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Reflexes increased | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Sleep disorder | 2 (1.4%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Somnolence | 15 (10.5%) | 20 (14.8%) | 9 (9.9%) | 9 (9.5%) |
| Speech disorder | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | 2 (2.1%) |
| Thinking abnormal | 5 (3.5%) | 1 (0.7%) | 3 (3.3%) | 1 (1.1%) |
| Tremor | 5 (3.5%) | 2 (1.5%) | 4 (4.4%) | 4 (4.2%) |
| Vertigo | 4 (2.8%) | 3 (2.2%) | 3 (3.3%) | 2 (2.1%) |
| Weakness | (0.0%) | 2 (1.5%) | (0.0%) | 1 (1.1%) |
| Respiratory | ||||
| Apnea | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Asthma | 6 (4.2%) | 5 (3.7%) | 5 (5.5%) | 2 (2.1%) |
| Bronchitis | 2 (1.4%) | 5 (3.7%) | 6 (6.6%) | 2 (2.1%) |
| Carcinoma of lung | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Cough increased | 62 (43.4%) | 38 (28.1%) | 38 (41.8%) | 21 (22.1%) |
| Dry nasal | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Dyspnea | 60 (42.0%) | 33 (24.4%) | 25 (27.5%) | 25 (26.3%) |
| Epistaxis | 10 (7.0%) | 8 (5.9%) | 16 (17.6%) | 4 (4.2%) |
| Hemoptysis | 1 (0.7%) | (0.0%) | 2 (2.2%) | (0.0%) |
| Hiccup | 4 (2.8%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Hyperventilation | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Hypoxia | 4 (2.8%) | 1 (0.7%) | (0.0%) | 5 (5.3%) |
| Laryngismus | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Laryngitis | (0.0%) | (0.0%) | 3 (3.3%) | 1 (1.1%) |
| Larynx edema | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Lung disorder | 12 (8.4%) | 4 (3.0%) | 7 (7.7%) | 7 (7.4%) |
| Lung edema | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Pharyngitis | 43 (30.1%) | 25 (18.5%) | 20 (22.0%) | 13 (13.7%) |
| Pleural disorder | (0.0%) | (0.0%) | 2 (2.2%) | 1 (1.1%) |
| Pleural effusion | 9 (6.3%) | 4 (3.0%) | 6 (6.6%) | 5 (5.3%) |
| Pneumonia | 9 (6.3%) | 4 (3.0%) | 2 (2.2%) | 2 (2.1%) |
| Pneumothorax | 2 (1.4%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Respiratory disorder | 3 (2.1%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Rhinitis | 31 (21.7%) | 21 (15.6%) | 20 (22.0%) | 5 (5.3%) |
| Sinusitis | 18 (12.6%) | 8 (5.9%) | 19 (20.9%) | 7 (7.4%) |
| Sputum change | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Sputum increased | 1 (0.7%) | 2 (1.5%) | (0.0%) | 1 (1.1%) |
| Vocal cord paralysis | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Voice alteration | 5 (3.5%) | (0.0%) | 4 (4.4%) | 3 (3.2%) |
| Skin and appendages | ||||
| Acne | 4 (2.8%) | 1 (0.7%) | 10 (11.0%) | 3 (3.2%) |
| Alopecia | 83 (58.0%) | 80 (59.3%) | 51 (56.0%) | 53 (55.8%) |
| Contact dermatitis | (0.0%) | (0.0%) | 2 (2.2%) | 1 (1.1%) |
| Cutaneous moniliasis | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Dry skin | 1 (0.7%) | 7 (5.2%) | 4 (4.4%) | 4 (4.2%) |
| Eczema | 2 (1.4%) | (0.0%) | (0.0%) | (0.0%) |
| Exfoliative dermatitis | 2 (1.4%) | 1 (0.7%) | 3 (3.3%) | 2 (2.1%) |
| Fungal dermatitis | 6 (4.2%) | 5 (3.7%) | 3 (3.3%) | (0.0%) |
| Furunculosis | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Herpes simplex | 10 (7.0%) | 11 (8.1%) | 11 (12.1%) | 3 (3.2%) |
| Herpes zoster | 4 (2.8%) | 4 (3.0%) | 4 (4.4%) | 2 (2.1%) |
| Maculopapular rash | 2 (1.4%) | 3 (2.2%) | 3 (3.3%) | 1 (1.1%) |
| Melanosis | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Nail disorder | 6 (4.2%) | 5 (3.7%) | 4 (4.4%) | 1 (1.1%) |
| Pruritus | 11 (7.7%) | 8 (5.9%) | 13 (14.3%) | 12 (12.6%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Psoriasis | 1 (0.7%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Purpuric rash | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Pustular rash | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Rash | 38 (26.6%) | 23 (17.0%) | 35 (38.5%) | 17 (17.9%) |
| Seborrhea | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Skin discoloration | 7 (4.9%) | 3 (2.2%) | 2 (2.2%) | 1 (1.1%) |
| Skin disorder | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | 1 (1.1%) |
| Skin hypertrophy | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Skin melanoma | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Skin nodule | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Skin ulcer | 8 (5.6%) | 6 (4.4%) | 3 (3.3%) | 1 (1.1%) |
| Subcutaneous nodule | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Sweating | 13 (9.1%) | 10 (7.4%) | 7 (7.7%) | 3 (3.2%) |
| Urticaria | 2 (1.4%) | (0.0%) | 1 (1.1%) | 1 (1.1%) |
| Vesiculobullous rash | 1 (0.7%) | 1 (0.7%) | 3 (3.3%) | 1 (1.1%) |
| Special senses | ||||
| Abnormal vision | 11 (7.7%) | 3 (2.2%) | 6 (6.6%) | 3 (3.2%) |
| Amblyopia | 8 (5.6%) | 5 (3.7%) | 5 (5.5%) | 6 (6.3%) |
| Blepharitis | (0.0%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Blindness | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Cataract specified | 1 (0.7%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Conjunctivitis | 12 (8.4%) | 9 (6.7%) | 6 (6.6%) | 2 (2.1%) |
| Corneal lesion | (0.0%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Deafness | 2 (1.4%) | 3 (2.2%) | (0.0%) | 2 (2.1%) |
| Diplopia | 1 (0.7%) | 2 (1.5%) | 1 (1.1%) | 2 (2.1%) |
| Dry eyes | 3 (2.1%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Ear disorder | 2 (1.4%) | 2 (1.5%) | 1 (1.1%) | 1 (1.1%) |
| Ear pain | 4 (2.8%) | 1 (0.7%) | 3 (3.3%) | 1 (1.1%) |
| Eye disorder | 1 (0.7%) | 2 (1.5%) | (0.0%) | (0.0%) |
| Eye hemorrhage | 1 (0.7%) | 1 (0.7%) | (0.0%) | 1 (1.1%) |
| Eye pain | 1 (0.7%) | 2 (1.5%) | 2 (2.2%) | (0.0%) |
| Glaucoma | (0.0%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Hyperacusis | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Keratitis | (0.0%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Lacrimation disorder | 7 (4.9%) | 12 (8.9%) | 3 (3.3%) | (0.0%) |
| Otitis media | 3 (2.1%) | 2 (1.5%) | 3 (3.3%) | (0.0%) |
| Parosmia | 1 (0.7%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Photophobia | (0.0%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Ptosis | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Retinal artery occlusion | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Retinal disorder | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Strabismus | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Taste loss | 2 (1.4%) | (0.0%) | (0.0%) | 3 (3.2%) |
| Taste perversion | 16 (11.2%) | 18 (13.3%) | 5 (5.5%) | 3 (3.2%) |
| Tinnitus | 2 (1.4%) | 2 (1.5%) | 2 (2.2%) | 2 (2.1%) |
| Vestibular disorder | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Visual field defect | 1 (0.7%) | (0.0%) | 3 (3.3%) | (0.0%) |
| Vitreous disorder | 2 (1.4%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Urogenital | ||||
| Acute kidney failure | (0.0%) | (0.0%) | 1 (1.1%) | 1 (1.1%) |
| Albuminuria | 2 (1.4%) | (0.0%) | 1 (1.1%) | (0.0%) |
| Amenorrhea | 2 (1.4%) | 5 (3.7%) | 1 (1.1%) | (0.0%) |
| Breast carcinoma | 6 (4.2%) | 3 (2.2%) | 2 (2.2%) | 5 (5.3%) |
| Adverse Event Term | Trastuzumab + AC | AC Alone | Trastuzumab + Paclitaxel | Paclitaxel Alone |
|---|---|---|---|---|
| (N=143) | (N=135) | (N=91) | (N=95) | |
| Breast enlargement | 1 (0.7%) | 1 (0.7%) | (0.0%) | 1 (1.1%) |
| Breast neoplasm | 3 (2.14%) | 2 (1.5%) | 1 (1.1%) | (0.0%) |
| Breast pain | 8 (5.6%) | 7 (5.2%) | 2 (2.2%) | 6 (6.3%) |
| Cystitis | 1 (0.7%) | 3 (2.2%) | 1 (1.1%) | 1 (1.1%) |
| Dysmenorrhea | (0.0%) | (0.0%) | (0.0%) | 2 (2.1%) |
| Dyspareunia | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Dysuria | 6 (4.2%) | 7 (5.2%) | 3 (3.3%) | 3 (3.2%) |
| Fibrocystic breast | 2 (1.4%) | (0.0%) | (0.0%) | (0.0%) |
| Hematuria | 3 (2.1%) | 2 (1.5%) | 2 (2.2%) | 1 (1.1%) |
| Hydronephrosis | 2 (1.4%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Kidney failure | 1 (0.7%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Kidney function abnormal | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Kidney pain | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Leukorrhea | 6 (4.2%) | 1 (0.7%) | (0.0%) | 1 (1.1%) |
| Mastitis | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Menopause | 3 (2.1%) | (0.0%) | (0.0%) | (0.0%) |
| Menorrhagia | (0.0%) | 1 (0.7%) | 1 (1.1%) | 2 (2.1%) |
| Menstrual disorder | (0.0%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Metrorrhagia | 3 (2.1%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Nocturia | 1 (0.7%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Oliguria | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Papanicolau smear suspicious | (0.0%) | 1 (0.7%) | (0.0%) | (0.0%) |
| Polyuria | (0.0%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Urinary frequency | 5 (3.5%) | 8 (5.9%) | 1 (1.1%) | 1 (1.1%) |
| Urinary incontinence | 7 (4.9%) | 1 (0.7%) | 2 (2.2%) | 1 (1.1%) |
| Urinary retention | 2 (1.4%) | (0.0%) | (0.0%) | 1 (1.1%) |
| Urinary tract disorder | 1 (0.7%) | 1 (0.7%) | 1 (1.1%) | 1 (1.1%) |
| Urinary tract infection | 19 (13.3%) | 9 (6.7%) | 17 (18.7%) | 13 (13.7%) |
| Urinary urgency | 1 (0.7%) | 1 (0.7%) | 2 (2.2%) | (0.0%) |
| Urination impaired | 1 (0.7%) | (0.0%) | (0.0%) | (0.0%) |
| Urine abnormality | 2 (1.4%) | 1 (0.7%) | 1 (1.1%) | (0.0%) |
| Vaginal hemorrhage | (0.0%) | 2 (1.5%) | 1 (1.1%) | 2 (2.1%) |
| Vaginal moniliasis | 9 (6.3%) | 2 (1.5%) | 2 (2.2%) | 1 (1.1%) |
| Vaginitis | 7 (4.9%) | 8 (5.9%) | 5 (5.5%) | 1 (1.1%) |
Other Serious Adverse Events
The following other serious adverse events occurred in at least one of the 958 patients treated with trastuzumab in the MBC clinical trials conducted prior to market approval:
Body as a Whole: abdomen enlarged, allergic reaction, anaphylactoid reaction, ascites, carcinoma, cellulitis, chills and fever, death, dermatomyositis, hydrocephalus, necrosis, neoplasm, pelvic pain, radiation injury, sepsis, malaise
Cardiovascular: atrial fibrillation, cardiomyopathy, cardiovascular disorder, cerebrovascular accident, deep thrombophlebitis, heart arrest, heart failure, hemorrhage, hypotension, pericardial effusion, pulmonary embolus, thrombophlebitis, thrombosis, syncope, shock, supraventricular tachycardia, vascular disorder, ventricular arrhythmia
Digestive: colitis, dysphagia, esophageal hemorrhage, esophageal ulcer, gastritis, gastroenteritis, gastrointestinal disorder, gastrointestinal hemorrhage, hematemesis, hepatic coma, hepatic failure, hepatic neoplasia, hepatitis, hepatomegaly, ileus, intestinal obstruction, liver tenderness, pancreatitis, peptic ulcer hemorrhage, pseudomembranous colitis, rectal hemorrhage
Endocrine: hypothyroidism
Hematological: acute leukemia, coagulation disorder, lymphangitis, marrow depression, myeloid maturation arrest, pancytopenia
Metabolic: bilirubinemia, growth retardation, hypercalcemia, hyponatremia, hypoglycemia, hypomagnesemia, weight loss
Musculoskeletal: pathologic fracture, bone necrosis, myopathy
Nervous: ataxia, CNS neoplasia, confusion, convulsion, grand mal convulsion, manic reaction, thinking abnormal
Respiratory: apnea, asthma, hypoxia, laryngitis, lung disorder, lung edema, pleural effusion, pneumonia, pneumothorax, respiratory disorder
Skin: herpes zoster, skin ulceration, dry skin
Special Senses: amblyopia, deafness, retinal artery occlusion
Urogenital: breast carcinoma, breast neoplasm, cervical cancer, hematuria, hemorrhagic cystitis, hydronephrosis, kidney failure, kidney function abnormal, pyelonephritis, vaginal hemorrhage
When using in combination with pertuzumab and docetaxel, consult Product Monographs for pertuzumab and docetaxel for further information on these drugs.
Metastatic Gastric Cancer (MGC)
The ToGA trial (BO18255) is a randomized, open-label multicentre, phase III study of trastuzumab in combination with a fluoropyrimidine (FP) and cisplatin versus chemotherapy alone in patients with HER2 positive MGC. There were only 3.4% of patients in each treatment group with locally advanced cancer. The majority of patients had metastatic disease.
The adverse drug reactions that occurred with the incidence of at least 1% in the ToGA (BO18255) study are presented in Table 21.
Table 21 Adverse Drug Reactions With Incidence Rate ≥ 1% in ToGA (BO18255)
FP/Cisplatin (FP) N = 290 No. (%) | Trastuzumab/ FP/Cisplatin (H+FP) N = 294 No. (%) | |
|---|---|---|
| Blood and lymphatic system disorders | ||
| Neutropenia | 165 (57) | 157 (53) |
| Anemia | 61 (21) | 81 (28) |
| Thrombocytopenia | 33 (11) | 47 (16) |
| Febrile neutropenia | 8 (3) | 15 (5) |
| Leukopenia | 11 (4) | 11 (4) |
| Cardiac disorders | ||
| Palpitations | 2 (<1) | 6 (2) |
| Ear and labyrinth disorders | ||
| Deafness | 1 (<1) | 8 (3) |
| Eye disorders | ||
| Lacrimation increased | 2 (<1) | 5 (2) |
| Gastrointestinal disorders | ||
| Nausea | 184 (63) | 197 (67) |
| Vomiting | 134 (46) | 147 (50) |
| Diarrhea | 80 (28) | 109 (37) |
| Constipation | 93 (32) | 75 (26) |
| Stomatitis | 43 (15) | 72 (24) |
FP/Cisplatin (FP) N = 290 No. (%) | Trastuzumab/ FP/Cisplatin (H+FP) N = 294 No. (%) | |
|---|---|---|
| Abdominal pain | 42 (14) | 46 (16) |
| Abdominal pain upper | 15 (5) | 27 (9) |
| Dyspepsia | 16 (6) | 18 (6) |
| Hemorrhoids | 3 (1) | 5 (2) |
| Abdominal discomfort | 3 (1) | 3 (1) |
| Dry mouth | 2 (<1) | 4 (1) |
| General disorders and administration site conditions | ||
| Fatigue | 82 (28) | 102 (35) |
| Asthenia | 53 (18) | 55 (19) |
| Pyrexia | 36 (12) | 54 (18) |
| Mucosal inflammation | 18 (6) | 37 (13) |
| Edema | 25 (9) | 22 (7) |
| Edema peripheral | 12 (4) | 17 (6) |
| Chills | - | 23 (8) |
| Chest pain | 4 (1) | 8 (3) |
| Malaise | 6 (2) | 6 (2) |
| Pain | 4 (1) | 5 (2) |
| Infusion related reaction | - | 3 (1) |
| Hepatobiliary disorders | ||
| Hepatic function abnormal | 3 (1) | 3 (1) |
| Infections and infestations | ||
| Nasopharyngitis | 17 (6) | 37 (13) |
| Upper respiratory tract infection | 10 (3) | 15 (5) |
| Pneumonia | 2 (<1) | 9 (3) |
| Cystitis | 1 (<1) | 5 (2) |
| Pharyngitis | 2 (<1) | 4 (1) |
| Respiratory tract infection | 3 (1) | 3 (1) |
| Infection | 2 (<1) | 3 (1) |
| Influenza | 1 (<1) | 4 (1) |
| Immune system disorders | ||
| Hypersensitivity | 3 (1) | 6 (2) |
| Injury, poisoning and procedural complications | ||
| Contusion | 2 (<1) | 3 (1) |
| Investigations | ||
| Weight decreased | 40 (14) | 69 (23) |
| Hemoglobin decreased | 2 (<1) | 7 (2) |
| Platelet count decreased | 6 (2) | 1 (<1) |
| Neutrophil count decreased | 3 (1) | 3 (1) |
| Metabolism and nutrition disorders | ||
| Anorexia | 133 (46) | 135 (46) |
| Hyperkalaemia | 3 (1) | - |
| Musculoskeletal and connective tissue disorders | ||
| Back pain | 15 (5) | 12 (4) |
| Pain in extremity | 7 (2) | 4 (1) |
| Arthralgia | 2 (<1) | 7 (2) |
| Musculoskeletal pain | 4 (1) | 5 (2) |
| Myalgia | 3 (1) | 4 (1) |
| Muscular weakness | 3 (1) | 2 (<1) |
| Muscle spasms | 1 (<1) | 3 (1) |
FP/Cisplatin (FP) N = 290 No. (%) | Trastuzumab/ FP/Cisplatin (H+FP) N = 294 No. (%) | |
|---|---|---|
| Musculoskeletal chest pain | 3 (1) | 1 (<1) |
| Neck pain | 1 (<1) | 3 (1) |
| Nervous system disorders | ||
| Dizziness | 28 (10) | 31 (11) |
| Peripheral sensory neuropathy | 24 (8) | 23 (8) |
| Neuropathy peripheral | 21 (7) | 24 (8) |
| Dysgeusia | 14 (5) | 28 ( 0) |
| Headache | 19 (7) | 14 (5) |
| Paraesthesia | 9 (3) | 9 (3) |
| Lethargy | 8 (3) | 6 (2) |
| Peripheral motor neuropathy | 6 (2) | 8 (3) |
| Tremor | 5 (2) | 3 (1) |
| Renal and urinary disorders | ||
| Renal impairment | 39 (13) | 47 (16) |
| Nephropathy toxic | 12 (4) | 18 (6) |
| Renal failure acute | 2 (<1) | 3 (1) |
| Renal failure | 1 (<1) | 3 (1) |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 17 (6) | 19 (6) |
| Dyspnea | 16 (6) | 9 (3) |
| Epistaxis | 9 (3) | 13 (4) |
| Rhinorrhea | 2 (<1) | 6 (2) |
| Psychiatric disorders | ||
| Insomnia | 20 (7) | 24 (8) |
| Depression | 5 (2) | 4 (1) |
| Anxiety | 5 (2) | 3 (1) |
| Sleep disorder | 3 (1) | 2 (<1) |
| Skin and subcutaneous tissue disorders | ||
| Palmar-plantar erythrodysaesthesia syndrome | 64 (22) | 75 (26) |
| Alopecia | 27 (9) | 32 (11) |
| Rash | 12 (4) | 16 (5) |
| Nail disorder | 6 (2) | 13 (4) |
| Dry skin | 4 (1) | 10 (3) |
| Pruritus | 3 (1) | 8 (3) |
| Urticaria | 3 (1) | 3 (1) |
| Vascular disorders | ||
| Hypertension | 7 (2) | 11 (4) |
| Hypotension | 6 (2) | 6 (2) |
Adverse Events of Special Interest
The following subsections provide additional detail regarding adverse reactions observed in clinical trials in EBC, MBC, MGC, or post-market experience.
Cardiac (EBC and MBC)
For a description of cardiac toxicities see WARNINGS AND PRECAUTIONS.
Cardiac (Metastatic Gastric Cancer)
In the ToGA (BO18255) study, at screening, the median LVEF value was 64% (range 48%-90%) in the FP arm and 65% (range 50%-86%) in the FP+H arm. At baseline, a LVEF value of 50% or more (measured by ECHO or MUGA) was required at study entry.
The majority of the LVEF decreases noted in ToGA (BO18255) were asymptomatic, with the exception of one patient in the trastuzumab-containing arm whose LVEF decrease coincided with cardiac failure.
Table 22 Summary of LVEF Change from Baseline ToGA (BO18255)
| LVEF Decrease: Lowest Post-screening Value | FP/Cisplatin (N = 290) (% of patients in each treatment arm) | Trastuzumab/FP/Cisplatin (N = 294) (% of patients in each treatment arm) | ||
|---|---|---|---|---|
| * LVEF decrease of ≥10% to a value of < 50% | 1.1% | 4.6% | ||
| Absolute Value < 50% | 1.1% | 5.9% | ||
* LVEF decrease of ≥10% to a value of ≥50% | 11.8% | 16.5% | ||
| * Only includes patients whose method of assessment at that visit is the same as at their initial assessments (F + C, n = 187 and H +FC, n = 237) | ||||
Table 23 Cardiac Adverse Events ToGA (BO18255)
FP/Cisplatin (N = 290) (% of patients in each treatment arm) | Trastuzumab/FP/Cisplatin (N = 294) (% of patients in each treatment arm) | |||
|---|---|---|---|---|
| Total Cardiac Events | 6% | 6% | ||
| ≥Grade 3 NCI-CTC AE V3.0 | *3% | **1% | ||
* 9 patients experienced 9 Events ** 4 patients experienced 5 Events | ||||
Infusion-Associated Symptoms
During the first infusion with trastuzumab, chills and/or fever are observed commonly in patients. Other signs and/or symptoms may include nausea, vomiting, pain, rigors, headache, cough, dizziness, rash, asthenia and hypertension. The symptoms are usually mild to moderate in severity, and occur infrequently with subsequent infusions of trastuzumab. The symptoms can be treated with an analgesic/antipyretic such as meperidine or acetaminophen, or an antihistamine such as diphenhydramine (see DOSAGE AND ADMINISTRATION).
Interruption of the infusion was infrequent. Some adverse reactions to infusions of trastuzumab including dyspnea, hypotension, wheezing, bronchospasm, tachycardia, reduced oxygen saturation and respiratory distress can be serious and potentially fatal (see WARNINGS AND PRECAUTIONS).
Hematological Toxicity
In a randomized controlled clinical trial in MBC (H0648g), WHO Grade 3 or 42 hematological toxicity was observed in 63% of patients treated with trastuzumab and an anthracycline plus cyclophosphamide compared to an incidence of 62% in patients treated with anthracycline/cyclophosphamide combination without trastuzumab. There was an increase in WHO Grade 3 or 4 hematological toxicity in patients treated with the combination of trastuzumab
2 WHO Grade 3 Hematological Toxicity: Hemoglobin – 6.5-7.9 g/100 mL, 65-79 g/L, 4.0-4.9 mmol/L, Leukocytes (1000/mm3) – 1.0-1.9, Granulocytes (1000/mm3) – 0.5-0.9, Platelets (1000/mm3) – 25-49.
WHO Grade 4 Hematological Toxicity: Hemoglobin – <6.5 g/100 mL, <65 g/L, <4.0 mmol/L, Leukocytes (1000/mm3) – <1.0, Granulocytes (1000/mm3) – <0.5, Platelets (1000/mm3) – <25.
and paclitaxel compared with patients receiving paclitaxel alone (34% vs. 21%).
In a randomized, controlled trial in patients with MBC conducted in the post-market setting, hematological toxicity was also increased in patients receiving trastuzumab and docetaxel, compared with docetaxel alone (32% grade 3/4 neutropenia versus 22%, using NCI-CTC criteria). The incidence of febrile neutropenia/neutropenic sepsis was also increased in patients treated with trastuzumab plus docetaxel (23% versus 17% for patients treated with docetaxel alone), see WARNINGS AND PRECAUTIONS.
Anemia and Leukopenia
In a randomized controlled clinical trial in MBC, an increased incidence of anemia and leukopenia was observed in the treatment group receiving trastuzumab and chemotherapy (26.9% and 41%), especially in the trastuzumab and AC subgroup (35.0% and 51.7%), compared with the treatment group receiving chemotherapy alone (18.7% and 26.5%). The majority of these cytopenic events were mild or moderate in intensity, reversible, and none resulted in discontinuation of therapy with trastuzumab.
Hematologic toxicity is infrequent following the administration of trastuzumab as a single agent, with an incidence of Grade 3 toxicities for WBC, platelets, hemoglobin all < 1%. No Grade 4 toxicities were observed.
In study B-31, the incidence of grade 3 to 5 anemia was comparable between the trastuzumab + chemotherapy and the chemotherapy alone arm (3.2% versus 3.1%). The incidence of grade 3 to 5 leukopenia was lower in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone (10.0% versus 10.7%).
In study N9831, the incidence of grade 3 to 5 anemia was comparable between the trastuzumab+ chemotherapy and the chemotherapy alone arm (0.2% versus 0.0%). The incidence of grade 3 to 5 leukopenia was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone (8.5% versus 7.7%).
In study BCIRG-006 the incidence of grade 3 or 4 anemia according to the NCI-CTC v 2.0 classification was comparable between the AC-T arm (4.4%) and the AC-TH arm (4.9%). The TCH arm had a higher incidence of grade 3 or 4 anemia (8.3%) as would be expected from the known toxicity profile of carboplatin. The incidence of grade 3 or 4 leukopenia according to the NCI-CTC v 2.0 classification (52.7% AC-T, 61.5% AC-TH, and 49.9% TCH) was similar in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
Thrombocytopenia
In HERA study in EBC, the incidence of thrombocytopenia (0.1% vs. 0.06%) was comparable between patients randomized to trastuzumab + chemotherapy and those randomized to chemotherapy alone.
In study B-31 in EBC, the incidence of thrombocytopenia (2.2% in the AC→TH arm vs. 2.5% in the AC→T arm) was lower in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
In study N9831 in EBC, the incidence of thrombocytopenia (0% in the AC→TH arm vs. 0.3% in the AC→T arm) was lower in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
In study BCIRG-006 in EBC, the incidence of grade 3 or 4 thrombocytopenia (5.6% in the AC→T arm, 6.8% in the AC→TH arm) was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone. The incidence of grade 3 or 4 thrombocytopenia in the TCH arm (9.8%) was higher as would be expected from the known toxicity profile of carboplatin.
Neutropenia
In HERA study in EBC, the incidence of neutropenia (0.4% vs. 0.2%) was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
In study B-31 in EBC, the incidence of febrile neutropenia (3.8% in the AC→TH arm vs. 4.7% in the AC→T arm) was lower in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone. The incidence of neutropenia (grade 3-5) (10.4% in the AC→TH arm vs. 9.9% in the AC→T arm) was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
In study N9831 in EBC, the incidence of febrile neutropenia (5.9% in the AC→TH arm vs. 4.3% in the AC→T arm) was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone. The incidence of neutropenia (grade 3-5) (29.5% in the AC→TH arm vs. 27.3% in the AC→T arm) was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone.
In study BCIRG-006, the incidence of febrile neutropenia according to NCI-CTC v 2.0 classification (10.9% in the AC→TH arm, 9.6% in the TCH arm, and 9.3% in the AC→T arm) was comparable between patients randomized to trastuzumab + chemotherapy and with those randomized to chemotherapy alone. The incidence of grade 3 or 4 neutropenia according to the NCI-CTC v 2.0 classification (72.5% in the AC→TH arm, 67.0% in the TCH arm, and 64.6% in the AC→T arm) was comparable between patients randomized to trastuzumab + chemotherapy and with those randomized to chemotherapy alone.
Infection
In three studies in EBC, the incidence of infection was higher in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone (HERA: 29% vs. 12%; B-31: 32% AC→TH vs. 28% AC→T; N9831: 7.3% AC→TH vs. 4.7% AC→T).
In study BCIRG-006 in EBC, the overall incidence of infection (all grades) was higher with the addition of trastuzumab to AC→T but not to TCH [44% (AC→TH), 37% (TCH), 38% (AC→T)]. The incidences of NCI-CTC Grade 3-4 infection were similar [25% (AC→TH), 21% (TCH), 23% (AC→T)] across the three arms.
In a randomized controlled clinical trial in MBC, an increased incidence of infections, primarily mild upper respiratory infections of minor clinical significance or catheter infections, was observed in patients receiving trastuzumab in combination with chemotherapy.
In the ToGA (BO18255) study in MGC, infections and infestations were reported in 20 % of patients in the FP arm vs. 32% in the FP+H arm. The major contributors to the higher incidence of infections and infestations in the trastuzumab arm were nasopharyngitis (6% in the FP arm vs.
13% in the FP+H arm) and upper respiratory tract infection (3% vs. 5%).
Hypersensitivity Reactions Including Anaphylaxis and Pulmonary Events
In HERA study, there were 4 cases of interstitial pneumonitis in trastuzumab-treated patients compared to none in the control arm.
The incidence of allergic reactions (chemotherapy alone versus trastuzumab + chemotherapy: 3.7% versus 3.4% in study B-31 and 1.2% versus 0.3% in study N9831) was comparable between the two treatment arms in both studies.
The incidence of pulmonary events in the original analysis for adjuvant studies (16.1% versus 7.8% in study B-31 and 4.1% versus 1.4% in study N9831) was higher in patients randomized to trastuzumab + chemotherapy versus chemotherapy alone. The most common pulmonary event was dyspnea. The majority of these events were mild to moderate in intensity. Fatal pulmonary events were reported in 4 patients in the trastuzumab + chemotherapy arm. Only 1 of these patients actually received trastuzumab. The cause of death in these 4 patients was cardio-respiratory arrest, bronchopneumonia, respiratory insufficiency, and pneumonia accompanied by neutropenic fever. Pneumonitis/lung infiltrates were reported in 20 patients who participated in either adjuvant clinical trial. Twelve of these 20 patients had received trastuzumab + chemotherapy. The etiology of pneumonitis/lung infiltrates was possible hypersensitivity/inflammation reaction (n= 4), pneumonia (n=5), radiation therapy toxicity (n=1) ad unknown etiology (n= 2).
In the most recent safety update for the NSABP B-31 and NCCTG N9831 Joint Analysis report (median follow-up of 8.1 years for the AC→TH group and 8.5 years for the AC→T group), the incidences of pulmonary adverse events reported in study B-31 were 17.5% in the AC→T + H group and 8.5% in the AC→T group. Likewise, the incidences of pulmonary adverse events reported in study N9831 were 4.0% in the AC→T + H group and 1.7% in the AC→T group.
These results confirm the results from the original analysis, which showed a higher rate of pulmonary events in the trastuzumab patients. Dyspnea remained the most common pulmonary adverse event reported in both studies. Dyspnea can be a result of cardiac left ventricular dysfunction.
Pneumonitis/pulmonary infiltrates were reported in 26 patients in both studies (7 in study B-31, 18 in study N9831) and17 of these patients were in the AC→T + H group. All 7 patients in study B-31 were in the AC→T + H group, and 10 of the patients in study N9831 were in the AC→T + H group. There were 8 patients with this adverse event in study N9831 in the AC→T group
In study BCIRG-006, the incidence of allergic reactions according to the NCI-CTC v 2.0 classification was 9.4%, 12.3% and 14.9% in AC→T, AC→TH and TCH arms, respectively.
Among women receiving trastuzumab for treatment of MBC in a randomized controlled clinical trial, the incidence of pulmonary toxicity was also increased in patients randomized to trastuzumab + chemotherapy compared with those randomized to chemotherapy alone (e.g. dyspnea 36.3% vs. 25.2%, lung disorder 8.1% vs. 4.8%, lung edema 0.4% vs. 0%, pleural effusion 6.4% vs. 3.9%).
In the post-market setting, severe hypersensitivity reactions (including anaphylaxis), infusion reactions, and pulmonary adverse events have been reported. These events include anaphylaxis, angioedema, bronchospasm, hypotension, hypoxia, dyspnea, lung infiltrates, pleural effusions, non-cardiogenic pulmonary edema, and acute respiratory distress syndrome (see WARNINGS AND PRECAUTIONS).
Thrombosis/Embolism
In study BCIRG-006, the incidence of all grades thrombosis/embolism according to the NCI- CTC v 2.0 classification was higher in patients receiving trastuzumab in combination with docetaxel and carboplatin (TCH) (3.2%) compared to the AC→TH group (2.0%) and AC→T group (1.7%). The incidence of thrombosis/embolism, grade 3 (deep vein thrombosis, requiring anticoagulant) and grade 4 (embolic event including pulmonary embolism) combined, was higher in patients receiving trastuzumab in combination with docetaxel and carboplatin (TCH) (2.7%) compared to the AC→TH group (1.8%) and AC→T group (1.5%).
In study B-31, thrombosis/embolism (all grades) was reported in 3.8% of patients randomized to trastuzumab + chemotherapy versus 2.7% of patients randomized to the chemotherapy alone arm. In study N9831, thrombosis/embolism (all grades) was reported in 1.9% of patients randomized to trastuzumab + chemotherapy versus 2.9% of patients randomized to chemotherapy alone.
The incidence of thrombotic adverse events was also higher in patients receiving trastuzumab and chemotherapy compared to chemotherapy alone in a randomized clinical trial in MBC setting (2.1% vs. 0%).
Diarrhea
Among women receiving adjuvant therapy for breast cancer, the incidence of NCI-CTC (v 2.0) Grade 3-5 diarrhea (2.5% vs. 2.6% [B-31]) and of NCI-CTC Grade 3-5 diarrhea (3.4% vs. 0.7% [N9831]), and of Grade 1-4 diarrhea (7% vs. 1% [HERA]) were commonly higher in patients receiving trastuzumab as compared to controls. In BCIRG-006 study, the incidence of Grade 3-4 diarrhea was higher [5.6% AC-TH, 5.4% TCH vs. 3.1% AC-T] and of Grade 1-4 was higher [51% AC-TH, 63% TCH vs. 43% AC-T] among women receiving trastuzumab.
Of patients treated with trastuzumab as a single agent for the treatment of MBC, 25% experienced diarrhea. An increased incidence of diarrhea, primarily mild to moderate in severity, was observed in patients receiving trastuzumab in combination with chemotherapy.
In the ToGA (BO18255) study in MGC, 109 patients (37%) participating in the trastuzumab- containing treatment arm versus 80 patients (28%) in the comparator arm experienced any grade diarrhea. Using NCI-CTCAE v3.0 severity criteria, the percentage of patients experiencing grade ≥ 3 diarrhea was 4% in the FP arm vs. 9% in the FP+H arm.
Hepatic and Renal Toxicity
In a randomized controlled clinical trial in MBC, WHO Grade 3 or 43 hepatic toxicity was observed in 6% of patients treated with trastuzumab and an anthracycline plus cyclophosphamide compared with an incidence of 8% in patients treated with anthracycline/cyclophosphamide combination without trastuzumab. Hepatic toxicity was less
3 WHO Grade 3 Hepatic Toxicity: Bilirubin – 5.1-10 x N, Transaminases (ASAT/ALAT) – 5.1-10 x N, Alkaline Phosphatase – 5.1-10 x N, where N is the upper limit of normal of population under study.
WHO Grade 4 Hepatic Toxicity: Bilirubin – >10 x N, Transaminases (ASAT/ALAT) – >10 x N, Alkaline Phosphatase – >10 x N, where N is the upper limit of normal of population under study.
frequently observed among patients receiving trastuzumab and paclitaxel than among patients receiving paclitaxel (7% vs. 15%).
WHO Grade 3 or 4 hepatic toxicity was observed in 12% of patients following administration of trastuzumab as a single agent. This toxicity was associated with progression of disease in the liver in 60% of these patients.
The toxicity grading scale used for HERA, NSABP B-31, NCCTG N9831, and BCIRG-006 studies in the adjuvant treatment of EBC was the NCI-CTC v 2.0. The definitions for grade 3 and 4 elevations of serum creatinine were: grade 3 (> 3.0 to 6.0 X ULN) and grade 4 (> 6.0 X ULN).
The frequencies of grade 3-4 elevated serum creatinine reported in each study are shown, by treatment arm in
Table 24.
Table 24 Frequencies of Grade 3-4 Elevated Serum Creatinine in Studies of the Adjuvant Treatment of Early Breast Cancer
| Study | Treatment Arm | Grade 3-4 Serum Creatinine Elevation | ||
|---|---|---|---|---|
| Regimen | N | N | % | |
| HERA | observation only | 1708 | 0 | 0.0 |
| 1-year Trastuzumab | 1678 | 0 | 0.0 | |
| NSABP B-31 | AC→T | 885 | 1 | 0.1 |
| AC→TH | 1030 | 0 | 0.0 | |
| NCCTG N9831 | AC→T | 766 | 0 | 0.0 |
| AC→TH | 969 | 0 | 0.0 | |
| BCIRG-006 | AC→T | 1041 | 6 | 0.6 |
| AC→TH | 1077 | 3 | 0.3 | |
| TCH | 1056 | 1 | 0.1 | |
A higher incidence of renal impairment (13% in the FP arm vs. 16% in the FP+H arm) and toxic nephropathy (4% in the FP arm vs. 6% in the FP+H arm) was reported in the ToGA (BO18255) trial in MGC using NCI-CTCAE (v 3.0) criteria. Grade ≥3 renal toxicity was higher in patients receiving trastuzumab than those in the chemotherapy alone arm (3% and 2% respectively).
NCI-CTCAE (v 3.0) grade ≥3 adverse events in the Hepatobiliary Disorders SOC: Hyperbilirubinaemia was reported in 1% of patients receiving trastuzumab compared to <1% in patients in the chemotherapy alone arm.
Blood and Lymphatic System Disorders
In the ToGA (BO18255) study in MGC, the total percentages of patients who experienced an AE of ≥ grade 3 NCI-CTC AE v3.0 categorised under the SOC of Blood and Lymphatic System Disorders were 38% in the FP arm and 40% in the FP + H arm.
Table 25 Blood and Lymphatic System Disorders SOC: The Most Frequently Reported AEs of Grade ≥ 3 With Incidence Rate ≥ 1%
FP/Cisplatin (N = 290) (% of patients in each treatment arm) | Trastuzumab/FP/Cisplatin (N = 294) (% of patients in each treatment arm) | |
|---|---|---|
| Neutropenia | 30% | 27% |
| Anaemia | 10% | 12% |
| Febrile Neutropenia | 3% | 5% |
| Thrombocytopenia | 3% | 5% |
FP/Cisplatin (N = 290) (% of patients in each treatment arm) | Trastuzumab/FP/Cisplatin (N = 294) (% of patients in each treatment arm) | |
|---|---|---|
| Leukopenia | <1% | 2% |
9.2 Less Common Clinical Trial Adverse Reactions
Early Breast Cancer (EBC)
Listing of Adverse Events with Incidence Rate of < 1% in Study B-31
(Final analysis after median follow-up of 8.1 years in the AC - T+H group)
Allergy/immunology: allergy-other, autoimmune reaction
Auditory/hearing: hearing-other, inner ear/hearing, middle ear/hearing
Blood/bone marrow: hematologic-other, hemolysis, transfusion: platelets, transfusion: pRBC (packed red blood cells)
Cardiovascular (arrhythmia): arrythmia-other, nodal/junctional arrythmia/dysrhythmia, palpitations, sinus tachycardia, supraventricular arrhythmias*, vasovagal episode, ventricular arrhythmia,
Cardiovascular (general): cardiac troponin I (cTnI), cardiac-ischemia/infarction*, circulatory or cardiac-other, hypotension, pericardial effusion/pericarditis, peripheral arterial ischemia, phlebitis (superficial), visceral arterial ischemia (non-myocardial),
Coagulation: coagulation-other, prothrombin time (PT)
Constitutional symptoms: constitutional symptoms-other, rigors/chills*, weight loss
Dermatology/skin: bruising (in absence of thrombocytopenia), dermatitis, dry skin, erythema multiforme, flushing, hand-foot skin reaction, injection site reaction, pigmentation changes, urticaria (hives, welts, wheals), wound non-infectious
Endocrine: endocrine-other, feminization of male, hypothyroidism, syndrome of inappropriate anti-diuretic hormone (SIADH)
Gastrointestinal: colitis, duodenal ulcer, dysphagia, dysphagia-esophageal, flatulence, gastric ulcer, gastritis, mouth dryness, mucositis due to radiation, pancreatitis, proctitis, salivary gland changes, sense of smell
Hemorrhage: CNS hemorrhage/bleeding, epistaxis, hematuria*, hemorrhage/bleeding without thrombocytopenia, melena/GI bleeding, petechiae/purpura, rectal bleeding/hematochezia,
Hepatic: alkaline phosphatase*, bilirubin*, GGT (gamma-glutamyl transpeptidase), hepatic enlargement, hepatic-other, hypoalbuminemia
Infection/febrile neutropenia: catheter-related infection
Lymphatics: lymphatics-other
Metabolic/laboratory: amylase, CPK (creatinine phosphokinase), hypocalcemia, hypokalemia, hypercholesterolemia, hyperkalemia, hypertriglyceridemia, hypomagnesemia, hyponatremia, hypophosphatemia, lipase, metabolic-other
Musculoskeletal: arthritis, muscle weakness, osteonecrosis
Neurology: arachnoiditis/meningismus/radiculitis, CNS cerebrovascular ischemia*, confusion, cognitive disturbance/learning problems, delusions, depressed level of consciousness, extrapyramidal/involuntary movement/, restlessness, leukoencephalopathy, memory loss, neurologic-other, neuropathy-cranial, personality/behavioral, seizure(s), speech impairment, tremor, vertigo
Not coded: raw term unknown
Ocular/visual: cataract, glaucoma, conjunctivitis, ocular-other, vision-double vision (diplopia), vision-flashing lights/floaters, vision-photophobia
Pain: dysmenorrhea, dyspareunia, earache (otalgia), pain due to radiation, pelvic pain, pleuritic pain, rectal or perirectal pain (proctalgia), tumour pain
Pulmonary: acute respiratory distress syndrome (ARDS), hypoxia, pleural effusion (non-malignant), pneumonitis/pulmonary infiltrates, pneumothorax, pulmonary fibrosis, voice changes/stridor/larynx
Radiation morbidity: radiation-other
Renal/genitourinary: bladder spasms, creatinine, incontinence, proteinuria, renal failure, renal/genitourinary-other, ureteral obstruction
Sexual/reproductive function: libido, sexual/reproductive function-other
*AE term is itemized on the AE CRF.
Listing of Adverse Events with Incidence Rate of < 1% in Study N9831 (Final analysis after median follow-up of 8.1 years in the AC - T+H group)
Auditory/hearing: inner ear/hearing
Blood/bone marrow: bone marrow cellularity, hemoglobin (HGB)*, platelets*, transfusion: platelets, transfusion: pRBCS (packed red blood cells)
Cardiovascular (arrhythmia): arrythmia-other, sinus bradycardia, sinus tachycardia, supraventricular arrhythmias, vasovagal episode, ventricular arrhythmia
Cardiovascular (general): circulatory or cardiac-other, hypotension, pericardial effusion/pericarditis, phlebitis (superficial), visceral arterial ischemia (non-myocardial)
Constitutional symptoms: fever (in the absence of neutropenia), rigors/chills, weight gain, weight loss
Dermatology/skin: dermatitis, erythema multiforme, hand-foot skin reaction, injection site reaction, photosensitivity, radiation dermatitis, rash/desquamation, skin other, wound-infectious
Endocrine: endocrine-other, hypothyroidism, syndrome of inappropriate anti-diuretic hormone (SIADH)
Gastrointestinal: anorexia, colitis, constipation, dehydration, diarrhea with prior colostomy*, dyspepsia, GI-other, ileus, stomatitis/pharyngitis*
Hemorrhage: CNS hemorrhage/bleeding, hemorrhage/bleeding with thrombocytopenia
Hepatic: SGOT (AST) (serum glutamic oxaloacetic transaminase), SGPT (ALT) serum glutamic pyruvic transaminase
Lymphatics: lymphatics*
Metabolic/laboratory: hypoglycemia, hypokalemia, hyponatremia
Musculoskeletal: arthritis
Neurology: ataxia (incoordination), CNS cerebrovascular ischemia, confusion, dizziness/lightheadedness, hallucinations, insomnia, memory loss, mood alteration-anxiety/agitation, mood alteration-depression, speech impairment, syncope (fainting)
Ocular/visual: conjunctivitis
Pain: abdominal pain or cramping, bone pain, dyspareunia, headache, neuropathic pain, pain-other, pleuritic pain
Pulmonary: acute respiratory distress syndrome (ARDS), apnea, cough, FEV1, hypoxia, pleural effusion (non-malignant), pulmonary fibrosis, pulmonary-other
Renal/genitourinary: dysuria (painful urination), fistula or genitourinary fistula, renal failure, renal/genitourinary-other, urinary frequency/urgency
Sexual/reproductive function: irregular menses (change from baseline)
*AE term is itemized on the AE CRF.
Listing of Adverse Events with Incidence Rate of < 1% in in Study BCIRG-006 (5 Year Follow Up) According to NCI-CTC Classification v 2.0
Allergy/immunology: vasculitis
Auditory/hearing: external auditory canal
Blood/bone marrow: leukocytes (total WBC), platelets, transfusion: platelets, transfusion: pRBCS (packed red blood cells)
Cardiovascular (general): CNS cerebrovascular ischemia, hypertension, hypotension, phlebitis (superficial), thrombosis/embolism, cardiac- ischemia/infarction, edema, myocarditis
Cardiovascular (arrhythmia): sinus tachycardia, vasovagal episode, conduction abnormality/ atrioventricular heart block, sinus bradycardia, ventricular arrhythmia (PVCs/bigeminy/trigeminy/ventricular tachycardia)
Dermatology/skin: photosensitivity, radiation recall reaction (reaction following chemotherapy in the absence of additional radiation therapy that occurs in a previous radiation port), urticaria (hives, welts, wheals).
Gastrointestinal: colitis, duodenal ulcer (requires radiographic or endoscopic documentation), dysphagia-esophageal related to radiation, gastric ulcer (requires radiographic or endoscopic documentation), dyspepsia/heartburn
Hemorrhage: hematemesis, hematuria (in the absence of vaginal bleeding), hemoptysis, hemorrhage/bleeding without grade 3 or 4 thrombocytopenia, melena/GI bleeding, petechiae/purpura (hemorrhage/bleeding into skin or mucosa)
Hepatic: alkaline phosphatase, bilirubin, GGT (gamma - glutamyl transpeptidase), hepatic pain, hypoalbuminemia, SGOT (AST) (serum glutamic oxaloacetic transaminase), SGPT (ALT) (serum glutamic pyruvic transaminase)
Endocrine: cushingoid appearance (e.g., moon face with or without buffalo hump, centripetal obesity, cutaneous striae), hypothyroidism
Metabolic/laboratory: hypercalcemia, hypercholesterolemia, hyperkalemia, hypernatremia, hypertriglyceridemia, hyperuricemia, hypocalcemia, hypoglycemia, hyponatremia
Musculoskeletal: arthritis, myositis (inflammation/damage of muscle)
Neurology: arachnoiditis/meningismus/radiculitis, ataxia (incoordination), depressed level of consciousness, extrapyramidal/involuntary movement/ restlessness, hallucinations, mood alteration- euphoria, neuropathy-cranial, personality/behavioral, seizure(s), speech impairment (e.g., dysphasia or aphasia)
Ocular/visual: cataract, glaucoma, middle ear/hearing, vision- double vision (diplopia), vision- flashing lights/floaters, vision- night blindness (nyctalopia), vision-photophobia
Pain: dysmenorrhea, dyspareunia, pain due to radiation, pelvic pain, pleuritic pain, pain due to radiation, rectal or perirectal pain (proctalgia), chest pain (non-cardiac and non-pleuritic)
Pulmonary: apnea, FEV1, hiccoughs (hiccups, singultus), pleural effusion (non-malignant), pulmonary fibrosis, pneumonitis/pulmonary infiltrates, pneumothorax, dyspnea (shortness of breath)
Renal/genitourinary: bladder spasms, creatinine, proteinuria, renal failure, urinary retention, urine color change (not related to other dietary or physiologic cause e.g., bilirubin, concentrated urine, hematuria)
Listing of Adverse Events with Incidence Rate of < 1% in in Study BCIRG-006 (5 Year Follow Up) According to COSTART Classification
Body as a whole: abdomen enlarged, abdominal pain, abscess, aggravation reaction, allergic reaction, ascites, asthenia, body odor, cellulitis, chest pain substernal, chills, collagen disorder, granuloma, halitosis, headache, hernia, hormone level altered, hydrocephalus, hypothermia, immune system disorder, infection, infection fungal, infection parasitic, injection site edema, injection site hemorrhage, injection site inflammation, injection site reaction, lab test abnormal, malaise, mucous membrane disorder, neck rigidity, necrosis, neoplasm, pelvic pain, peritonitis, photosensitivity reaction, radiation injury, rheumatoid arthritis, scleroderma, viral infection
Cardiac adverse events (body as a whole): chest pain substernal, face edema, pain, angina pectoris
Cardiovascular system: aortic stenosis, aphthous stomatitis, arrhythmia, arteriosclerosis, bigeminy, bradycardia, bundle branch block, cardiomyopathy, cardiospasm, cardiovascular disorder, carotid occlusion, cerebrovascular accident, cheilitis, congestive heart failure, coronary artery disorder, coronary occlusion, dyspnea, electrocardiogram abnormal, endocarditis, extrasystoles, heart arrest, heart failure, heart malformation, hyperkinesia, hyperlipemia, hypokinesia, hypotension, hypertonia, left heart failure, myocardial ischemia, pallor, palpitation, pericarditis, peripheral vascular disorder, spider angioma, supraventricular extrasystoles, supraventricular tachycardia, syncope, T inverted, tachycardia, thrombophlebitis, varicose vein, vascular anomaly, vascular disorder, venous pressure increased, ventricular extrasystoles, peripheral edema
Digestive system: cholecystitis, cholelithiasis, cirrhosis of liver, colitis, constipation, diarrhea, dysphagia, eructation, esophageal hemorrhage, fecal incontinence, gamma glutamyl transpeptidase increased, gastritis, gastroenteritis, gastrointestinal disorder, gastrointestinal hemorrhage, gingivitis, glossitis, hepatitis, hepatomegaly, increased appetite, jaundice, liver function tests abnormal, liver necrosis, liver tenderness, melena, mouth ulceration, nausea, oral moniliasis, perforated stomach ulcer, periodontal abscess, proctitis, rectal hemorrhage, sialadentitis, stomach atony, stomatitis, tongue discoloration, tongue disorder, tongue edema, tooth disorder, tooth malformation, vomiting
Endocrine system: diabetes mellitus, endocrine disorder, goiter, hyperthyroidism, thyroid disorder
Hemic and lymphatic system: aplastic anemia, ecchymosis, hemolysis, hypochromic anemia, leukopenia, lymphadenopathy, macrocytic anemia, myeloproliferative disorder, pancytopenia, petechia, purpura, thrombocytopenia
Metabolic and nutritional disorders: acidosis, albuminuria, bun increased, electrolyte abnormality, enzymatic abnormality, generalized edema, healing abnormal, hypercalcemia, hypercholesteremia, hyperlipemia, hypoglycemia, hypophosphatemia, hypoproteinemia, hypovelemia, lactic dehydrogenase increased, liver fatty deposit, respiratory alkalosis, thirst, uremia, weight loss
Musculoskeletal system: arthritis, arthrosis, bone disorder, bone pain, bursitis, generalized spasm, myalgia, myasthenia, myositis, osteomyelitis, tendinous contracture, tenosynovitis
Nervous system: abnormal dreams, abnormal gait, agitation, amnesia, anxiety, ataxia, CNS stimulation, coma, delirium, depression, dizziness, dry mouth, dysautonomia, emotional liability, facial paralysis, grand mal convulsion, hyperesthesia, hyperkinesia, hypesthesia, hypokinesia, ileus, incoordination, increased salivation, myelitis, myoclonus, nervousness, neuralgia, nystagmus, paresthesia, peripheral neuritis, reflexes decreased, somnolence, thinking abnormal, tremor, trismus, vasodilatation, apnea
Respiratory system: asthma, atelectasis, bronchitis, cough increased, dyspnea, hemoptysis, hiccup, hyperventilation, hypoxia, laryngismus, laryngitis, larynx edema, lung disorder, lung edema, lung fibrosis, pleural disorder, pneumonia, pneumothorax, respiratory disorder, sputum increased, application site reaction
Skin and appendages: dry skin, eczema, erythema multiforme, exfoliative dermatitis, fungal dermatitis, furunculosis, hair disorder, herpes zoster, hirsutism, ichthyosis, maculopapular rash, psoriasis, pustular rash, skin benign neoplasm, skin carcinoma, skin discoloration, skin granuloma, skin hypertrophy, skin nodule, skin ulcer, sweating, vesiculobullous rash
Special senses: abnormality of accommodation, blepharitis, blindness, conjunctival edema, corneal lesion, deafness, ear disorder, extraocular palsy, eye disorder, eye hemorrhage, glaucoma, keratitis, lacrimation disorder, mydriasis, ophthalmitis, otitis media, parosmia, ptosis, pupillary disorder, refraction disorder, retinal vascular disorder, taste loss, taste perversion, tinnitus, vestibular disorder, vitreous disorder
Urogenital system: amenorrhea, breast carcinoma, breast enlargement, breast neoplasm, cervix disorder, cervix neoplasm, cystitis, dysmenorrhea, dyspareunia, dysuria, endometrial disorder, endometrial hyperplasia, female lactation, genital edema, kidney function abnormal, kidney pain, mastitis, menopause, menorrhagia, menstrual disorder, metrorrhagia, nocturia, oliguria, ovarian disorder, polyuria, ruptured uterus, toxic nephropathy, unintended pregnancy, urethritis, urinary frequency, urinary incontinence, urinary tract disorder, urinary tract infection, urine abnormality, uterine disorder, uterine fibroids enlarged, uterine hemorrhage, uterine neoplasm, vaginal hemorrhage, vaginal moniliasis, vaginitis, vulvovaginal disorder, vulvovaginitis
Metastatic Gastric Cancer (MGC)
Listing of Adverse Drug Reactions With Incidence Rate < 1% in ToGA (BO18255)
Cardiac disorders: arrhythmia, atrial fibrillation, atrial flutter, bradycardia, cardiac failure, left ventricular dyfunction
Eye disorders: dry eye
Gastrointestinal disorders: abdominal pain lower, haemorrhoidal haemorrhage, lip swelling
General disorders and administration site conditions: influenza like illness, mucous membrane disorder
Hepatobiliary disorders: hepatic failure, hepatitis toxic, hepatotoxicity, jaundice
Infections and infestations: bronchitis, cellulitis, herpes zoster, lower respiratory tract infection, lung infection, neutropenic sepsis, paronychia, rhinitis, sepsis, sinusitis, urinary tract infection
Investigations: alanine aminotransferase increased, aspartate aminotransferase increased, blood alkaline phosphatase increased, blood alkaline phosphatase increased, blood lactate dehydrogenase increased, blood potassium increased, blood pressure decreased, ejection fraction decreased, gamma-glutamyltransferase increased, transaminases increased, white blood cell count decreased
Metabolism and nutrition disorders: decreased appetite, fluid retention
Musculoskeletal and connective tissue disorders: arthritis, joint swelling
Nervous system disorders: neurotoxicity, paresis, somnolence, toxic neuropathy
Renal and urinary disorders: renal disorder
Respiratory, thoracic and mediastinal disorders: acute respiratory distress syndrome, hypoxia, pharyngeal edema, pleural effusion, pneumonitis
Skin and subcutaneous tissue disorders: acne, dermatitis, erythema, hyperhidrosis, rash macular, rash papular, rash pruritic
9.3 Post-Market Adverse Drug Reactions
Table 26 Adverse Reactions Reported in the Post-Market Setting
| System organ class | Adverse reaction |
|---|---|
| Infections and infestations | Cystitis |
| Neutropenic sepsis | |
| Blood and lymphatic system disorders | Hypoprothrombinemia |
| Immune thrombocytopenia | |
| Immune system disorders | Anaphylactoid reaction |
| Anaphylactic reaction | |
| Anaphylactic shock | |
| Metabolism and nutrition disorders | Tumour lysis syndrome |
| System organ class | Adverse reaction |
|---|---|
| Eye disorders | Madarosis |
| Cardiac disorders | Cardiogenic shock |
| Tachycardia | |
| Pericardial effusion | |
| Respiratory, thoracic and mediastinal disorders | Bronchospasm |
| Oxygen saturation decreased | |
| Respiratory failure | |
| Interstitial lung disease | |
| Lung infiltration | |
| Acute respiratory distress syndrome | |
| Respiratory distress | |
| Pulmonary fibrosis | |
| Hypoxia | |
| Laryngeal oedema | |
| Hepatobiliary disorders | Hepatocellular injury |
| Renal and urinary disorders | Glomerulonephropathy |
| Renal failure | |
| Pregnancy, puerperium and perinatal conditions | Pulmonary hypoplasia |
| Renal hypoplasia | |
| Oligohydramnios |
Adverse Events
Table 27 below indicates adverse events that have been reported in patients who have received trastuzumab.
Table 27 Adverse Events
| System organ class | Adverse Event |
|---|---|
| Infections and infestations | Meningitis |
| Bronchitis | |
| Blood and lymphatic system disorders | Leukaemia |
| Nervous system disorders | Cerebrovascular disorder |
| Lethargy | |
| Coma | |
| Ear and labyrinth disorders | Vertigo |
| Respiratory, Thoracic and Mediastinal system disorders | Hiccups |
| Dyspnea exertional | |
| Gastrointestinal disorders | Gastritis |
| Pancreatitis | |
| Musculoskeletal and connective tissue disorders | Musculoskeletal pain |
| Renal and urinary disorders | Dysuria |
| Reproductive system and breast disorders | Breast pain |
| General disorders and administration site conditions | Chest discomfort |
10 DRUG INTERACTIONS
10.1 Overview
There have been no formal drug interaction studies performed with trastuzumab in humans. Strong evidence for clinically significant interactions with concomitant medications used in clinical studies has not been observed.
10.2 Drug-Drug Interactions
Administration of paclitaxel in combination with trastuzumab resulted in a two-fold decrease in clearance of trastuzumab in a non-human primate study. In one clinical study, an apparent 1.5-fold increase in serum levels of trastuzumab was seen when trastuzumab was administered with paclitaxel. However this observation could not be confirmed using a population pharmacokinetic approach (see DETAILED PHARMACOLOGY: Clinical Pharmacokinetics).
A population pharmacokinetic method using data from phase I, phase II and pivotal phase III studies, was used to estimate the steady state pharmacokinetics in patients administered trastuzumab at a loading dose of 4 mg/kg followed by a 2 mg/kg maintenance dose administered weekly. The administration of concomitant chemotherapy (either anthracycline/ cyclophosphamide or paclitaxel) did not appear to influence the pharmacokinetics of trastuzumab.
Experience from phase III clinical trials suggests that there is a potential drug interaction between trastuzumab and anthracycline chemotherapy. However, the clinical pharmacokinetic profile of doxorubicin or epirubicin in the presence of trastuzumab has not been described to date, and the exact nature of this potential interaction has yet to be described.
When using in combination with pertuzumab and docetaxel, consult Product Monographs for pertuzumab and docetaxel for further information on these drugs.
11 ACTION AND CLINICAL PHARMACOLOGY
11.1 Mechanism of Action
Trastuzumab is a recombinant DNA-derived humanized monoclonal antibody that selectively targets the extracellular domain of the human epidermal growth factor receptor 2 protein (HER2). The antibody is an IgG1 isotype that contains human framework regions with complementarity-determining regions of a murine anti-p185 HER2 antibody that binds to human HER2.
The HER2 (or c-erbB2) proto-oncogene or c-erbB2 encodes for a single transmembrane spanning, receptor-like protein of 185 kDa, which is structurally related to the epidermal growth factor receptor. HER2 protein overexpression is observed in 25%-30% of primary breast cancers. Studies of HER2-positivity rates in gastric cancer (GC) using immunohistochemistry (IHC) and fluorescence in situ hybridization (FISH) or chromogenic in situ hybridization (CISH) have shown that there is a broad variation of HER2-positivity ranging from 6.8% to 34.0% for IHC and 7.1% to 42.6% for FISH A consequence of HER2 gene amplification is an increase in HER2 protein expression on the surface of these tumour cells, which results in a constitutively-activated HER2 protein. Studies indicate that patients whose tumours overexpress HER2 have a shortened disease-free survival compared to patients whose tumours do not overexpress HER2. HER2 protein overexpression can be determined using an immunohistochemistry-based assessment of fixed tumour blocks, ELISA techniques on tissue or serum samples or Fluorescence In Situ Hybridisation (FISH) technology. N.B., to date, only data derived from immunohistochemistry staining is relevant to treatment with trastuzumab (see WARNINGS AND PRECAUTIONS: Selection of Patients).
Trastuzumab has been shown, in both in vitro assays and in animals, to inhibit the proliferation of human tumour cells that overexpress HER2.
Trastuzumab is a mediator of antibody-dependent cell-mediated cytotoxicity (ADCC). In vitro, ADCC mediated by trastuzumab has been shown to be preferentially exerted on HER2 overexpressing cancer cells compared with cancer cells that do not overexpress HER2.
11.2 Pharmacokinetics
The pharmacokinetics of trastuzumab have been studied in breast cancer patients with metastatic disease. In phase I studies, short duration intravenous infusions of 10, 50, 100, 250 and 500 mg once weekly in patients demonstrated dose-dependent pharmacokinetics at doses below 100 mg. Mean half-lives increased and clearance decreased with increasing dose level. The half-life of trastuzumab averaged 1.7 and 12 days at the 10 and 500 mg dose levels, respectively.
Early Breast Cancer (EBC)/Metastatic Breast Cancer (MBC)
A population pharmacokinetic method, using data from phase I, phase II and pivotal phase III studies, was used to estimate the steady state pharmacokinetics in patients administered trastuzumab at a loading dose of 4 mg/kg followed by a weekly maintenance dose of 2 mg/kg. In this assessment, the typical clearance of trastuzumab was 0.225 L/day and the typical volume of distribution was 2.95 L, with a corresponding terminal half-life of 28.5 days (95% confidence interval, 25.5 - 32.8 days). The inter-patient variability in clearance and volume of distribution was 43% and 29% (co-efficient of variation), respectively. These values are lower than those estimated from the base model. Steady state weekly AUC of 578 mg•day/L, peak concentrations of 110 mg/L and trough concentrations of 66 mg/L should be reached by 143 days, or approximately 20 weeks. It should be noted that these values represent free and dimer complexes of trastuzumab as the assay utilized was unable to detect the trimer complex. Trastuzumab may persist in the circulation for approximately 24 weeks (range: 22-28 weeks, based on a 6-fold terminal elimination half-life value) (see WARNINGS AND PRECAUTIONS: Cardiovascular, Cardiotoxicity).
EBC patients administered an initial loading dose of 8 mg/kg followed by a three weekly maintenance dose of 6 mg/kg achieved steady state (see Table 28 below). These concentrations were comparable to those reported previously in patients with MBC.
Table 28 Summary of Trastuzumab Pharmacokinetic Parameters for Patients Enrolled into the Trastuzumab 1-year Treatment Group (sampled PK Population)
| PK Parameter | Cycle 18 (trastuzumab 1-year arm) | ||
|---|---|---|---|
| Mean ± SD (n) | |||
| Cmax (µg/mL) | 225 ± 30 (30) | ||
| Concentration – Day 21* (µg/mL) | 68.9 ± 14 (28) | ||
| Concentration – Day 42 (µg/mL) | 30.7 ± 14 (28) | ||
| AUC0-21d (day•µg/mL) | 2260 ± 340 (28) | ||
| AUC0-42d (day•µg/mL) | 3270 ± 560 (28) | ||
| Half-life (day) | 18.8 ± 7.2 (29) | ||
| * Day 21 concentration was calculated by linear interpolation from concentrations observed in patients on Days 14 and 28. | |||
Detectable concentrations of the circulating extracellular domain of the HER2 receptor (shed antigen) are found in the serum of some patients with HER2-overexpressing tumours. Patients with higher baseline shed antigen levels were more likely to have lower serum trough concentrations of trastuzumab, however, with weekly dosing, most patients with elevated shed antigen levels achieved target serum concentrations by week 6. Levels of shed antigen were only determined at baseline in the clinical trials. As a result, the available data are too limited to adequately characterize the interrelationship of HER2 overexpression and serum shed antigen concentrations.
Data suggest that the disposition of trastuzumab is not altered based on age or serum creatinine (up to 2.0 mg/dL or 176.8 μmol/L). No formal interaction studies have been performed.
Metastatic Gastric Cancer (MGC)
A population pharmacokinetic method, using data from the Phase III study ToGA (BO18255), was used to estimate the steady state pharmacokinetics in patients with MGC administered trastuzumab 3-weekly at a loading dose of 8 mg/kg followed by a 3-weekly maintenance dose of 6 mg/kg. In this assessment, the typical clearance of trastuzumab was 0.378 L/day and the typical volume of distribution was 3.91 L, with a corresponding equilibrium half-life of 12.2 days. The median predicted steady-state AUC values (over a period of 3 weeks at steady state) is equal to 1030 mg•day/L, the median steady-state Cmax is equal to 128 mg/L and the median steady-state Cmin values is equal to 23 mg/L. Steady state concentrations should be reached by 49 days, (four equilibrium half lives) or approximately 7 weeks.
Trastuzumab clearance in MGC patients is higher than that in MBC patients, leading to lower AUC, Cmax and Cmin at steady-state.
The estimated equilibrium half-life of trastuzumab was 12.2 days in the ToGA (BO18255) trial and 26.3 days for studies BO15935 and WO16229 (in MBC). The lower value in the ToGA (BO18255) trial was due to the increase in clearance in the MGC patients.
Special Populations and Conditions
Detailed pharmacokinetic studies in the elderly and those with renal or hepatic impairment have not been carried out.
12 STORAGE, STABILITY AND DISPOSAL
Vials of HERZUMA® (trastuzumab) are stable at 2°C - 8°C prior to reconstitution. Discard any vial that is past the expiry date indicated on the label. A vial of HERZUMA® reconstituted with BWFI, containing 1.1% benzyl alcohol, as supplied, is stable for 28 days after reconstitution when stored refrigerated at 2°C -8°C. Discard any remaining reconstituted solution after 28 days. If unpreserved SWFI (not supplied) is used, the reconstituted solution of HERZUMA® should be used immediately and any unused portion must be discarded. Do not freeze HERZUMA® that has been reconstituted.
The solution of HERZUMA® for infusion diluted in polyvinylchloride, polyethylene or polypropylene bags containing 0.9% Sodium Chloride Injection, USP, is physicochemically stable for up to 24 hours at temperatures up to 30°C prior to use. However, since diluted HERZUMA® contains no preservative, the reconstituted and diluted solution should be stored refrigerated (2°C -8°C). From a microbiological point of view, the infusion solution of HERZUMA® should be used immediately.
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided. Use established “collection systems”, if available in your location. Local requirements should be followed for the disposal process of unused/expired medicines.
13 SPECIAL HANDLING INSTRUCTIONS
Disposal of syringes/sharps
The following procedures should be strictly adhered to regarding the use and disposal of syringes and other medicinal sharps:
- Needles and syringes should never be reused.
- Place all used needles and syringes into a sharps container (puncture-proof disposable container).
- Dispose of the full container or waste material according to local requirements.
PART II: SCIENTIFIC INFORMATION
14 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Trastuzumab
Chemical name: Trastuzumab
Molecular formula and molecular mass: HC - C2192H3387N583O671S16, LC - C1032H1603N277O335S6 , 145,165 g/mol
Structural formula: Each heavy chain consists of 449 amino acids (without the C-terminal lysine residue) with 11 cysteine residues and each light chain consists of 214 amino acids with 5 cysteine residues.
Figure 1 Amino Acid Sequence of HERZUMA® (Trastuzumab)
| Heavy Chain |
|---|
1 E V Q L V E S G G G L V Q P G G S L R L S C A A S G F N I K D T Y I H W V R Q A P G K G L E W V A R 5 1 I Y P T N G Y T R Y A D S V K G R F T I S A D T S K N T A Y L Q M N S L R A E D T A V Y Y C S R W G 1 0 1 G D G F Y A M D Y W G Q G T L V T V S S A S T K G P S V F P L A P S S K S T S G G T A A L G C L V K 1 5 1 D Y F P E P V T V S W N S G A L T S G V H T F P A V L Q S S G L Y S L S S V V T V P S S S L G T Q T 2 0 1 Y I C N V N H K P S N T K V D K K V E P K S C D K T H T C P P C P A P E L L G G P S V F L F P P K P 2 5 1 K D T L M I S R T P E V T C V V V D V S H E D P E V K F N W Y V D G V E V H N A K T K P R E E Q Y N 1 3 0 1 S T Y R V V S V L T V L H Q D W L N G K E Y K C K V S N K A L P A P I E K T I S K A K G Q P R E P Q 3 5 1 V Y T L P P S R E E M T K N Q V S L T C L V K G F Y P S D I A V E W E S N G Q P E N N Y K T T P P V 4 0 1 L D S D G S F F L Y S K L T V D K S R W Q Q G N V F S C S V M H E A L H N H Y T Q K S L S L S P G K 2 |
| Light Chain |
1 D I Q M T Q S P S S L S A S V G D R V T I T C R A S Q D V N T A V A W Y Q Q K P G K A P K L L I Y S 5 1 A S F L Y S G V P S R F S G S R S G T D F T L T I S S L Q P E D F A T Y Y C Q Q H Y T T P P T F G Q 1 0 1 G T K V E I K R T V A A P S V F I F P P S D E Q L K S G T A S V V C L L N N F Y P R E A K V Q W K V 1 5 1 D N A L Q S G N S Q E S V T E Q D S K D S T Y S L S S T L T L S K A D Y E K H K V Y A C E V T H Q G 201 LSSPVTKSFN RGEC |
Physicochemical properties: HERZUMA® is a humanized IgG1 monoclonal antibody produced by mammalian (Chinese hamster ovary) cell suspension culture and purified by affinity and ion exchange chromatography including specific viral inactivation and removal procedures.
Product Characteristics
HERZUMA® is a recombinant humanized monoclonal immunoglobulin G1 antibody that has previously been demonstrated to bind to the extracellular domain (ECD) of the HER2 protein with high affinity, preventing activation of its intracellular tyrosine kinase.
15 COMPARATIVE CLINICAL TRIALS
15.1 Comparative Trial Design and Study Demographics
Clinical studies conducted to support similarity between HERZUMA® and the reference biologic drug, HERCEPTIN®, included:
- Study CT-P6 1.5, a randomized, double-blind, parallel-group, single-dose study to compare the PK, safety and immunogenicity of HERZUMA® and HERCEPTIN® in healthy volunteers
- Study CT-P6 3.2, a randomized, double-blind, parallel-group, active-controlled study to compare the efficacy and safety of HERZUMA® and HERCEPTIN® as neoadjuvant and adjuvant treatment in patients with HER2-positive early breast cancer.
An overview of the study design(s) and demographic characteristics of patients enrolled in each clinical study are presented in Table 29.
Table 29 Summary of trial design and patient demographics
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) (years) | Sex (n) |
| CT-P6 1.5 | Randomized, controlled, 2-arm, parallel-group, double-blind, single-dose study in healthy male subjects | HERZUMA® or HERCEPTIN®: 6 mg/kg, IV infusion for 90 minutes (± 5 minutes) | Randomized : 70 healthy subjects HERZUMA®: 35 HERCEPTIN®: 35 | HERZUMA®: 36.2 (20 - 55) HERCEPTIN ®: 34.1 (18 - 54) | Male: 70 |
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) (years) | Sex (n) |
| CT-P6 3.2 | Randomized, controlled, 2-arm, parallel-group, double-blind, multicentre, international study in patients with HER2-Positive EBC | Neoadjuvant Period HERZUMA® or HERCEPTIN®:
Docetaxel:
FEC:
Adjuvant Period HERZUMA® or HERCEPTIN®:
| Randomized: 562 EBC patients HERZUMA®: 278 HERCEPTIN®: 284 | HERZUMA®: 52.1 (24 - 79) HERCEPTIN ®: 52.0 (22 - 74) | Female : 562 |
The treatment of EBC patients with trastuzumab in the neoadjuvant setting is a model for assessing comparative clinical safety and efficacy; however, it is not an authorized indication in Canada.
15.2 Comparative Study Results
15.2.1 Comparative Bioavailability Studies
15.2.1.1 Pharmacokinetics
Comparability criteria were met for the PK parameters Cmax and AUCT as the point estimate for the ratio of the geometric means for HERZUMA® and HERCEPTIN® for Cmax and the 90% CI for the ratio of the geometric means for AUCT were within the acceptance margins of 80.0% to 125.0% (see Table 30).
Table 30 Analysis of PK Parameters (from measured data) in Study CT-P6 1.5
Trastuzumab (1 x 6 mg/kg) From measured data Geometric Mean Arithmetic Mean (CV %) |
| Parameter | HERZUMA® | HERCEPTIN® Roche (US) | Ratio (%) of Geometric LS Means | 90% CI of Ratio (%) |
|---|---|---|---|---|
AUCT (h·µg /mL) | 18183.7 18942.0 (19.3) | 18312.5 19121.2 (18.8) | 99.3 | 92.9 - 106.2 |
AUCI (h·µg /mL) | 19523.1 20307.5 (18.7) | 19709.4 20519.9 (17.6) | 99.1 | 93.0 - 105.5 |
Cmax (µg/mL) | 128.0 133.0 (17.9) | 132.5 137.3 (15.5) | 96.6 | 90.9 - 102.6 |
| Tmax (h)1 | 2.2 (43.3) | 2.6 (63.7) | ||
| T1/2 (h)1 | 189.3 (19.0) | 183.7 (20.4) | ||
Note: Number of subjects in each treatment group is 35. 1 Tmax and T1/2 are expressed as the arithmetic mean (CV %) only. AUCI: Area under the serum concentration-time curve from time 0 to infinity; AUCT: Area under the serum concentration-time curve from time 0 to the last measurable concentration; CI: Confidence interval; Cmax: Observed maximum serum concentration; LS: Least squares; PK: Pharmacokinetics; T1/2: Terminal half-life; Tmax: Time to maximum serum concentration. | ||||
15.2.2 Comparative Safety and Efficacy
15.2.2.1 Efficacy
Early Breast Cancer
Study CT-P6 3.2
The comparative efficacy and safety study CT-P6 3.2 was designed to rule out any clinically meaningful differences between HERZUMA® and HERCEPTIN®, both given in combination with docetaxel (Cycles 1 through 4) followed by 5-fluorouracil, epirubicin, and cyclophosphamide (FEC) (Cycles 5 through 8), in terms of efficacy as determined by pathological complete response (pCR), in patients with HER2-positive operable early breast cancer. The study included female patients 18 years of age or older with histologically confirmed and newly diagnosed breast cancer. Patients had HER2-positive status confirmed locally, defined as 3+ score by immunohistochemistry (IHC). When the IHC result was equivocal (defined as 2+ score), the patient had a positive fluorescence in situ hybridization (FISH) or a chromogenic in situ hybridization (CISH) result.
Demographic and baseline disease characteristics were similar between the HERZUMA® arm and the HERCEPTIN® arm with respect to age, race, height, weight, hormone receptor status and stage of disease. Overall, at screening 58.4% of study patients were hormone receptor positive (estrogen and/or progesterone), and the most frequently reported stage was Stage IIb (I: 10.0%, IIa: 29.2%, IIb: 36.7%, IIIa: 23.1%).
The primary efficacy endpoint was the proportion of patients achieving pCR, defined as the absence of invasive tumour cells in the breast and in axillary lymph nodes, regardless of the ductal carcinoma in situ (DCIS). The pCR was determined at the time of surgery, using hematoxylin and eosin evaluation of the resected specimen.
Comparability between HERZUMA® and HERCEPTIN® was demonstrated since the two-sided 95% confidence interval of the risk ratio for pCR after the Neoadjuvant Period was entirely contained within the pre-defined equivalence interval of [0.74 to 1.35].
Table 31 Pathological Complete Response (pCR) Rate after the Neoadjuvant Period in Study CT-P6 3.2 (ITT set)
| ITT set | |||||
|---|---|---|---|---|---|
HERZUMA® (n=278) | HERCEPTIN® (n=284) | ||||
| Primary endpoint: pCR | |||||
Response rate (%) (95% CI) | 120 (43.17%) (37.26 – 49.21) | 134 (47.18%) (41.26 – 53.17) | |||
Risk ratio estimate (95% CI)1 for risk ratio estimate | 0.9149 (0.7622 – 1.0981) | ||||
Abbreviations: CI, Confidence interval; ITT, intent-to-treat; pCR, pathological complete response 1 Asymptotic CI. | |||||
15.2.2.2 Safety
The types, frequency and severity of adverse events were comparable between the biosimilar and the reference biologic drug.
15.2.2.3 Immunogenicity
In Study CT-P6 1.5, no subject tested positive for ADAs at any time point. In Study CT-P6 3.2, no patients tested positive for ADAs at any post-baseline time points during the Neoadjuvant and Adjuvant Periods.
16 COMPARATIVE NON-CLINICAL PHARMACOLOGY AND TOXICOLOGY
16.1 Comparative Non-Clinical Pharmacodynamics
In vitro Studies
The active substance of HERZUMA®, trastuzumab, is a humanized monoclonal antibody that has been designed to bind to the ECD of the HER2 protein with high affinity. It was reported that trastuzumab exerts its action by several mechanisms including: prevention of receptor dimerization and activation, inhibition of signaling pathways, and downregulation of HER2 receptors. However, although trastuzumab has been shown to activate the complement cascade, no CDC activity against tumour cell lines occurred, probably due to the presence of regulatory proteins such as CD46, CD55 and CD59 on breast cancer cell lines.
In vitro similarity assays such as in vitro bioactivity (anti-proliferation activity), HER2 binding affinity, cell-based HER2 binding affinity, FcRn binding affinity, FcγRI/RIIa/RIIb/RIIIa(F/V type)/RIIIb binding affinity, ADCC activity (peripheral blood mononuclear cell [PBMC] and reporter assay) and C1q binding affinity have been performed to demonstrate similarity in the mode of action between HERZUMA® and HERCEPTIN® and it was concluded to be highly similar.
16.2 Comparative Toxicology
A repeat-dose toxicity study with intravenous administration of HERZUMA® and HERCEPTIN® once weekly for 4 weeks has been performed in both sexes cynomolgus monkeys (n=3/sex per group) at 2 doses of 14 and 42 mg/kg (Study ZIP0014). HERZUMA® and HERCEPTIN® were well tolerated and no test article-related changes was identified in mortality, body weights, electrocardiography (ECG), haematology, blood chemistry, urinalysis, organ weight, macroscopic findings and histopathological finding. Overall, the toxicological responses and the toxicokinetic profiles of treatment with HERZUMA® or HERCEPTIN® in cynomolgus monkeys were similar.
17 CLINICAL TRIALS – REFERENCE BIOLOGIC DRUG
Early Breast Cancer (EBC)
In the adjuvant treatment setting, trastuzumab was investigated in 4 large multicentre, randomized, trials:
|
The comparative efficacy and safety between different chemotherapy regimens (i.e. concurrent versus sequential, anthracycline containing versus non-anthracycline containing) was not studied.
Eligible patients in the four studies included women with operable, non-metastatic adenocarcinoma of the breast whose tumours overexpressed HER2 and who had either node-positive or high-risk node-negative disease. Definitions used in each protocol are shown in Table 32.
Table 32 Eligible Populations in EBC Studies, by TNM Categoriesa
| STUDY | AJCC TNM Version | T | N | M | Comment |
|---|---|---|---|---|---|
| HERA | Staging Manual 5th edition (1997) | ≥T1c, T2, T3, pT4 | N0, N1, N2, N3 | M0 | Prior (neo)adjuvant chemotherapy required. Prior radiotherapy required for nodal (axillary, internal mammary) or pT4 disease. |
| NSABP B-31 | Staging Manual 5th edition (1997) updated May 2003 to: Staging Manual 6th edition (2002) | clinical T1, T2, T3 updated May 2003 to: T1, T2, T3 (clinical and pathologic) | cN0, cN1 updated May 2003 to: cN0, cN1 and pN1, pN2a, pN3a | M0 | No prior chemotherapy or radiotherapy permitted. Whole breast irradiation required during study; partial breast or internal mammary radiation prohibited. |
| NCCTG N9831 | Staging Manual 5th edition (1997) | T1, T2, T3 | pN1, pN2 (minimum 1/6 nodes) | M0 | No prior chemotherapy or radiotherapy permitted. Breast + regional lymphatic irradiation during study, per radiotherapist. |
| T1c (ER-/PR- only), T2, T3 | pN0 (minimum sentinel node or 1/6 nodes) | ||||
| BCIRG-006 | Staging Manual 5th edition (1997) [not specified in protocol] | T1, T2, T3 | pN1, pN2 (minimum 1/6 nodes) | M0 | No prior chemotherapy or radiotherapy permitted. Breast + regional lymphatic irradiation during study, per radiotherapist. |
| ≥T2, or ER-/PR-, or nuclear Grade 2-3, or age <35 yrs | pN0 (minimum sentinel node or 1/6 nodes) | ||||
| aRequired for all studies: (1) invasive adenocarcinoma on histologic examination; (2) complete excision of primary tumour with tumour-free margins on histologic examination of specimens from definitive surgery; and (3) HER2 positive tumour | |||||
HERA
In the adjuvant setting, trastuzumab was investigated in HERA, a multicentre, randomized, trial designed to compare one and two years of three-weekly trastuzumab treatment versus observation in patients with HER2 positive EBC following surgery, established chemotherapy and radiotherapy (if applicable). In addition, a comparison of two years trastuzumab treatment versus one year trastuzumab treatment was performed, with the objective to assess the superiority of two years of trastuzumab treatment relative to one year of trastuzumab treatment. Breast tumour specimens were required to show HER2 overexpression (3+ by IHC) or gene amplification (by FISH) as determined at a central laboratory.
Patients assigned to receive trastuzumab were given an initial loading dose of 8 mg/kg, followed by 6 mg/kg every three weeks for either one or two years. One year of trastuzumab treatment was defined as 12 calendar months of treatment from day 1 of first administration and 18 infusions maximum. Two years of trastuzumab treatment were defined as 24 calendar months of treatment from day 1 of first administration and 35 infusions maximum.
The efficacy results from the HERA trial are summarized in Table 33. Please see ADVERSE REACTIONS and WARNINGS AND PRECAUTIONS: Cardiovascular/Cardiotoxicity/Early Breast Cancer for a summary of the HERA safety information.
Table 33 Efficacy Results from the HERA Trial: Results at 12 months* and 8 years** of median follow-up
Median follow-up 12 months | Median follow-up 8 years | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Parameter | Observation N=1693 | trastuzumab 1 Year N=1693 | Observation N=1697*** | trastuzumab 1 Year N=1702*** | |||||||
| Disease-free survival (DFS) | |||||||||||
| 219 (12.9%) | 127 (7.5%) | 570 (33.6%) | 471 (27.7%) | |||||||
| 1474 (87.1%) | 1566 (92.5%) | 1127 (66.4%) | 1231 (72.3%) | |||||||
| P-value versus Observation | <0.0001 | ||||||||||
| Hazard Ratio versus Observation | 0.54 | 0.76 | |||||||||
| Adjusted (99.9%) Confidence Interval**** | (0.38, 0.78) | ||||||||||
| Recurrence-free survival | |||||||||||
| 208 (12.3%) | 113 (6.7%) | 506 (29.8%) | 399 (23.4%) | |||||||
| 1485 (87.7%) | 1580 (93.3%) | 1191 (70.2%) | 1303 (76.6%) | |||||||
| Hazard Ratio versus Observation | 0.51 | 0.73 | |||||||||
| Distant disease-free survival | |||||||||||
| 184 (10.9%) | 99 (5.8%) | 488 (28.8%) | 399 (23.4%) | |||||||
| 1508 (89.1%) | 1594 (94.6%) | 1209 (71.2%) | 1303 (76.6%) | |||||||
| Hazard Ratio versus Observation | 0.50 | 0.76 | |||||||||
Median follow-up 12 months | Median follow-up 8 years | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Parameter | Observation N=1693 | trastuzumab 1 Year N=1693 | Observation N=1697*** | trastuzumab 1 Year N=1702*** | ||||||
| Overall survival (death) | ||||||||||
| 40 (2.4%) | 31 (1.8%) | 350 (20.6%) | 278 (16.3%) | ||||||
| 1653 (97.6%) | 1662 (98.2%) | 1347 (79.4%) | 1424 (83.7%) | ||||||
| Hazard Ratio versus Observation | 0.75 | 0.76 | ||||||||
*Co-primary endpoint of DFS of 1 year vs observation met the pre-defined statistical boundary of 0.0010. **Final analysis (including crossover of 52% of patients from the observation arm to trastuzumab). ***There is a discrepancy in the overall sample size due to a small number of patients who were randomized after the cut-off date for the 12-month median follow-up analysis. **** Adjusted (both for the interim analysis and the 2 comparisons of each trastuzumab arm (1 year and 2 years) vs. observation) confidence interval presented, to reflect the stopping boundary of p≤ 0.0010 of the comparison trastuzumab 1year vs. observation. The interval represents the 99.9% confidence interval. | ||||||||||
The efficacy results from the interim efficacy analysis crossed the protocol pre-specified statistical boundary of 0.0010 for the comparison of 1-year of trastuzumab vs. observation. After a median follow-up of 12 months, the hazard ratio (HR) for disease free survival (DFS) was 0.54 (adjusted 99.9% CI: 0.38, 0.78) which translates into an absolute benefit, in terms of a 2-year disease-free survival rate, of 7.6 percentage points (85.8% vs. 78.2%) in favour of the trastuzumab arm. Please see Figure 2.
A final analysis was performed after a median follow-up of 8 years, which showed that 1 year trastuzumab treatment is associated with a 24% risk reduction compared to observation only (HR = 0.76, unadjusted 95% CI: 0.67, 0.86). This translates into an absolute benefit in terms of an 8 year disease free survival rate of 6.4% in favour of 1 year trastuzumab treatment.
In this final analysis, superiority of 2 years trastuzumab treatment over 1 year trastuzumab treatment could not be demonstrated (DFS HR in the intent to treat (ITT) population of 2 years vs 1 year = 0.99 (unadjusted 95% CI: 0.87, 1.13), p-value = 0.90 and OS HR = 0.98 (unadjusted 95% CI: 0.83, 1.15); p-value = 0.78). The rate of secondary cardiac endpoints was increased in the 2-year treatment arm (8.1% vs 4.6% in the 1-year treatment arm). More patients experienced at least one grade 3 or 4 adverse event in the 2-year treatment arm (20.4%) compared with the 1-year treatment arm (16.3%).
Figure 2 Kaplan-Meier curve of Disease Free survival (After a Median Follow-up of 12 Months)
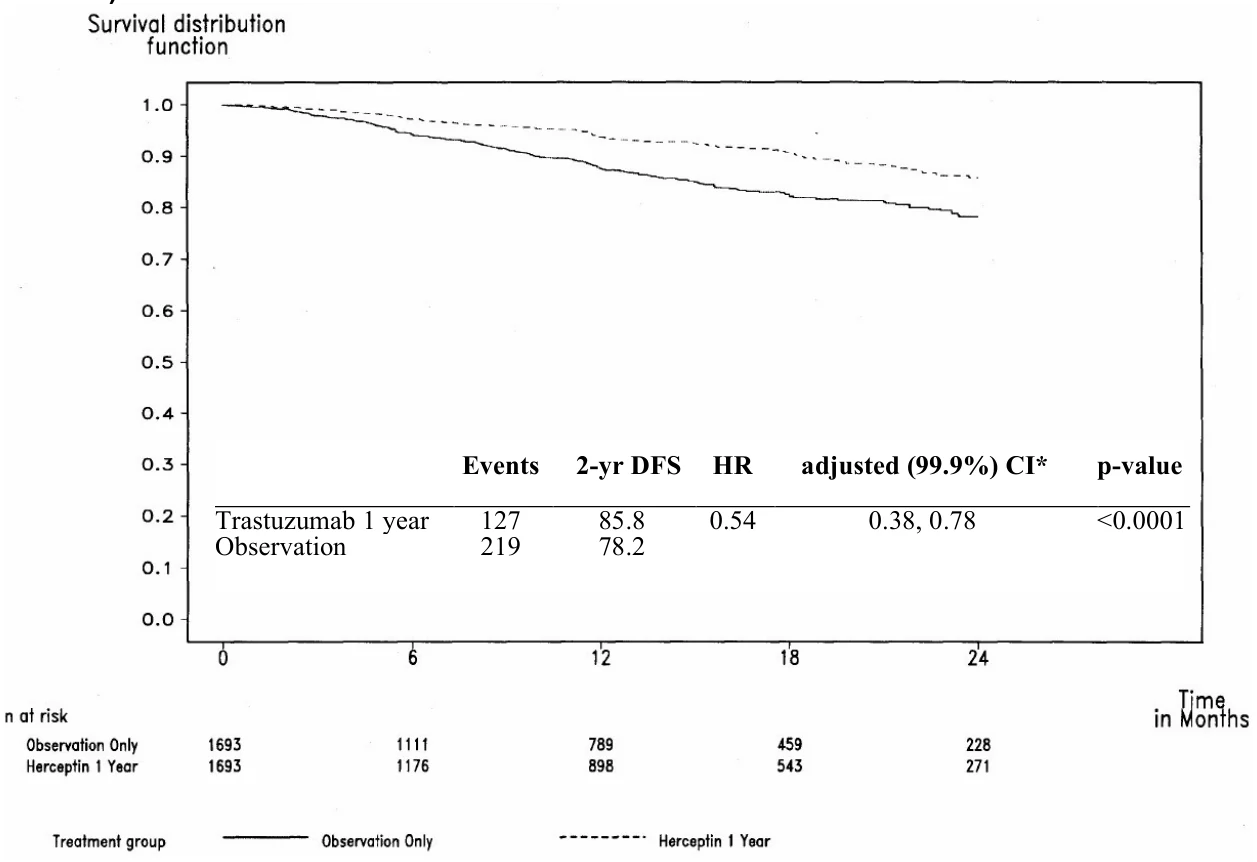
* Adjusted (both for the interim analysis and the 2 comparisons of each trastuzumab arm (1 year and 2 years) vs. observation) confidence interval presented, to reflect the stopping boundary of p≤ 0.0010 of the comparison trastuzumab 1year vs. observation. The interval represents the 99.9% confidence interval.
The benefit in disease-free survival was seen in all subgroups analysed (Please see Figure 3).
| Events | 2-yr DFS | HR | adjusted (99.9%) CI* | p-value | |
|---|---|---|---|---|---|
| Trastuzumab 1 year | 127 | 85.8 | 0.54 | 0.38, 0.78 | <0.0001 |
| Observation | 219 | 78.2 |
Figure 3 Risk Ratios and 95% Confidence Intervals for Disease-Free Survival by Subgroup (After a Median Follow-up of 12 Months)
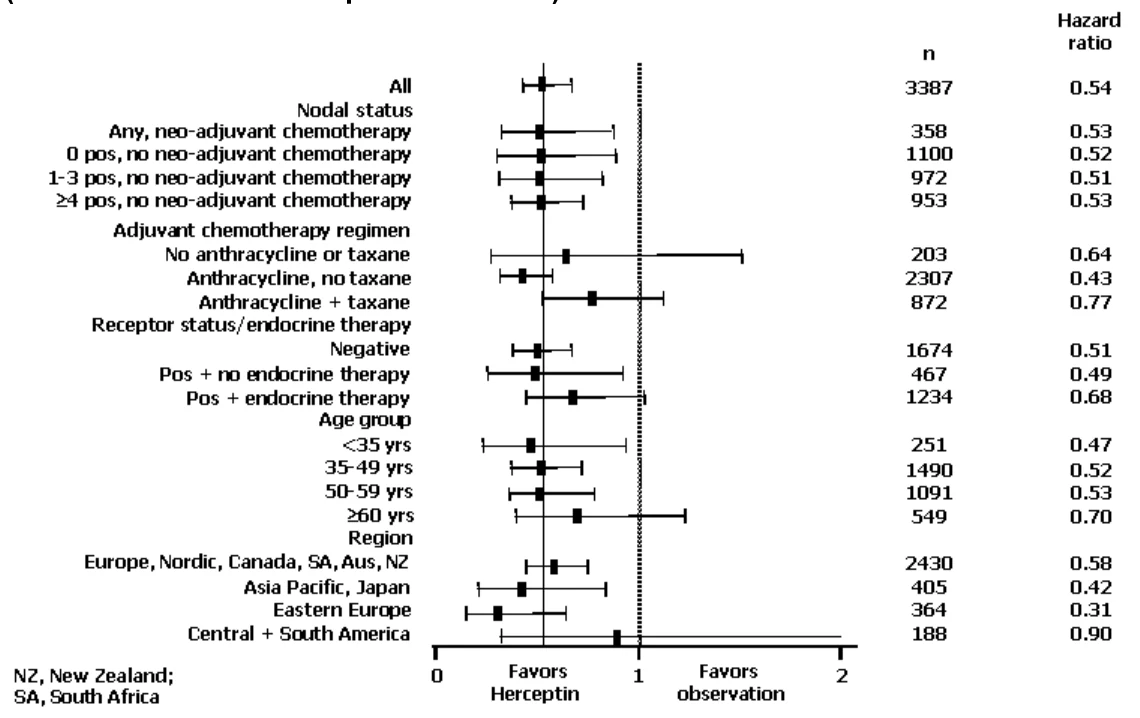
Note: 95%-CIs are not adjusted for multiple testing.
Twenty one (1.2%) patients in the trastuzumab arm and 16 (0.9) patients in the observation had CNS metastases as first site of relapse.
Figure 4 Kaplan-Meier Curve of Recurrence-Free Survival (After a Median Follow-up of 12 Months)
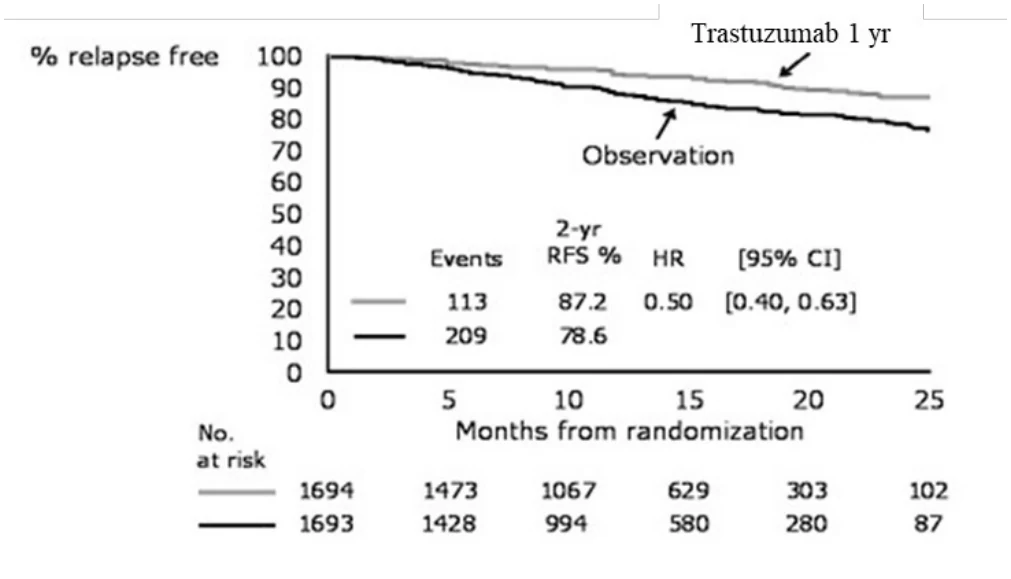
Note: 95%-CI is not adjusted for multiple testing.
Figure 5 Kaplan-Meier Curve of Distant-Disease-Free Survival (After a Median Follow-up of 12 Months)
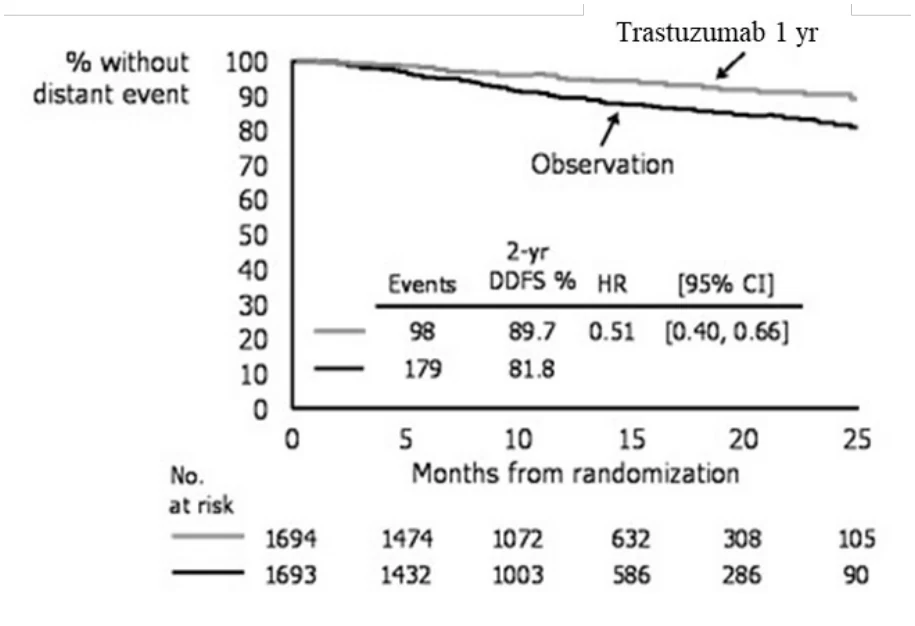
Note: 95%-CI is not adjusted for multiple testing.
Joint Analysis: NSABP B-31 and NCCTG N9831
Two cooperative group trials, NSABP B-31 and NCCTG N9831, evaluated the efficacy of incorporating trastuzumab into standard adjuvant systemic therapy in women with early stage, HER2 positive breast cancer. Breast tumour specimens were required to show HER2 overexpression (3+ by IHC) or gene amplification (by FISH). HER2 testing was verified by a central laboratory prior to randomization (N9831) or was required to be performed at a reference laboratory (B-31). Patients were randomized to receive doxorubicin and cyclophosphamide followed by paclitaxel (AC→T) or doxorubicin and cyclophosphamide followed by paclitaxel plus trastuzumab (AC→T + H). In both trials patients received four cycles (3 weeks per cycle) of doxorubicin, at 60 mg/m2 IV push, concurrently with IV cyclophosphamide at 600 mg/m2 over 20–30 minutes. Paclitaxel was administered weekly (80mg/m2) or every 3 weeks (175mg/m2) for a total of 12 weeks in NSABP B-31; paclitaxel was administered weekly (80mg/m2) for 12 weeks in NCCTG N9831. Trastuzumab was administered at a loading dose of 4 mg/kg load followed by 2 mg/kg IV weekly. Trastuzumab commenced with paclitaxel and continued for a total of 52 weeks in both trials. Disease-free survival was the pre-specified primary endpoint of the combined efficacy analysis of these studies.
A total of 3752 patients were evaluable for analysis of efficacy at the time of the definitive disease-free survival analysis. Median follow-up from the time of randomization was 1.8 years for the chemotherapy alone arm and 2.0 years for the trastuzumab + chemotherapy arm for both studies combined. Efficacy results are presented in Table 34 and Figure 6. For the primary endpoint, disease-free survival, addition of trastuzumab to chemotherapy reduced the risk of a first event by 52%. Please see ADVERSE REACTIONS and WARNINGS AND PRECAUTIONS: Cardiovascular/Cardiotoxicity/Early Breast Cancer for a summary of the Joint Analysis safety information.
Table 34 Joint Analysis: NSABP B-31 and NCCTG N9831 Efficacy Results at the Time of the Definitive Disease-Free Survival Analysis* (ITT population)
AC→Ta n=1880 | AC→T+trastuzumaba n=1872 | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| No. with Event | No. with Event | Hazard Ratio b (95% CI) | p-value c | ||||||
| Disease-free survival (DFS) | 261 | 133 | 0.48 (0.39 - 0.59) | < 0.0001 | |||||
| Overall survival (OS) | 92 | 62 | 0.67 | NSd | |||||
CI = confidence interval. Disease-free survival was defined as the time from randomization to recurrence, contralateral breast cancer or other second primary cancer, or death, whichever occurred first. Overall survival was defined as the time from randomization to death. * at median duration of follow up of 1.8 years for the patients in the AC→T arm and 2.0 years for patients in the AC→TH arm a NSABP B-31 and NCCTG N9831 regimens: doxorubicin and cyclophosphamide followed by paclitaxel (AC→T) or paclitaxel plus trastuxumab (AC→TH). b Hazard ratio estimated by Cox regression stratified by clinical trial, intended paclitaxel schedule, number of positive nodes, and hormone receptor status. c stratified log-rank test. d NS=non-significant. | |||||||||
Figure 6 Duration of Disease-Free Survival in Patients from the Joint Analysis: NSABP B-31 and NCCTG N9831
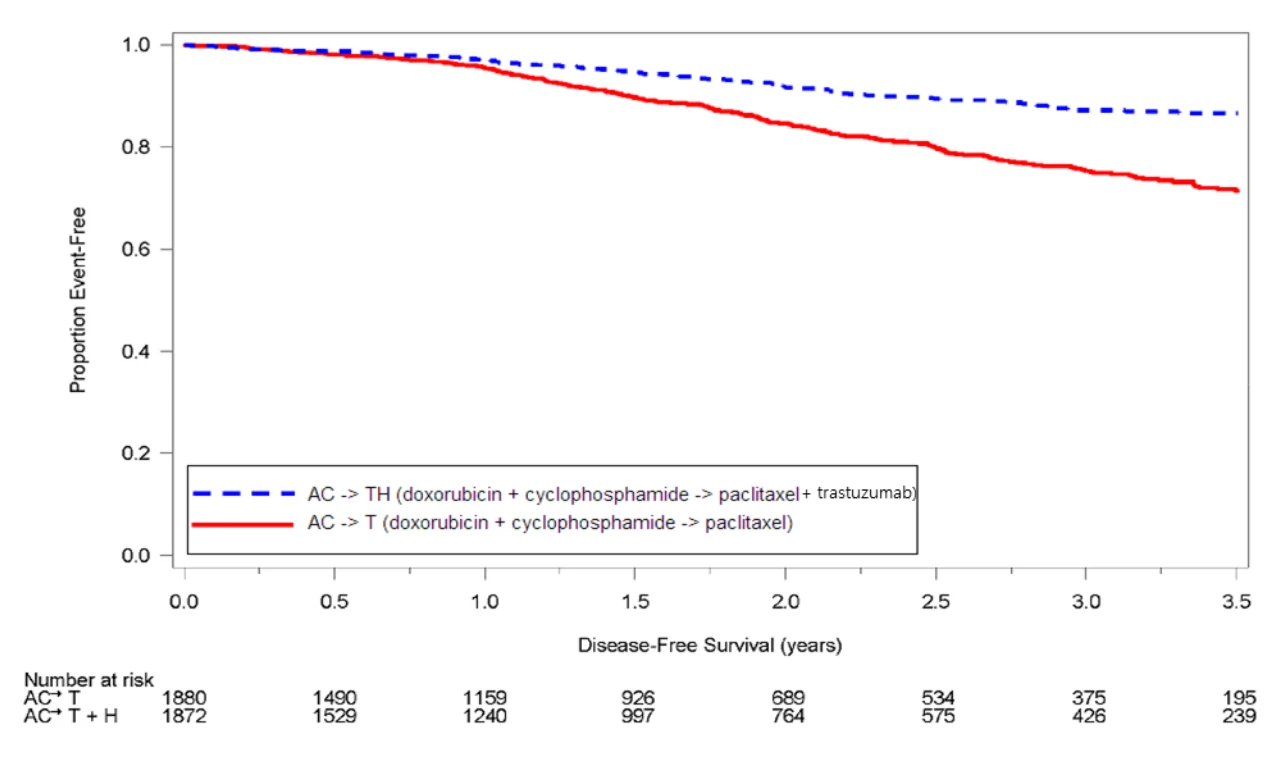
There were insufficient numbers of patients within each of the following subgroups to determine if the treatment effect was different from that of the overall patient population: Black, Hispanic, Asian/Pacific Islander patients, node-negative high-risk patients, and patients > 65 years of age.
The pre-planned final analysis of overall survival (OS) from the joint analysis of studies NSABP B-31 and NCCTG N9831 was performed when 707 deaths had occurred (median follow-up 8.3 years in the AC→T+H group). Treatment with AC→T+H resulted in a statistically significant improvement in OS compared with AC→T (stratified HR=0.64; 95.1% CI [0.55, 0.74]; log-rank p-value < 0.0001); formal boundary for statistical significance p-value=0.0245). At 8 years, the survival rate was estimated to be 86.9% in the AC→T+H arm and 79.4% in the AC→T arm, an absolute benefit of 7.4% (refer to Figure 7).
The final OS results from the joint analysis of studies NSABP B-31 and NCCTG N9831 are summarized in Table 35.
Table 35 Final Overall Survival Analysis from the Joint Analysis: NSABP B-31 and NCCTG N9831
AC→Ta n=2032 | AC→T+trastuzumaba n=2031 | |||||||
|---|---|---|---|---|---|---|---|---|
| No. with Event | No. with Event | Hazard Ratio (95.1% CI) | p-value | |||||
| Overall Survival | 418 (20.6%) | 289 (14.2%) | 0.64 (0.55–0.74) | < 0.0001 | ||||
| a NSABP B-31 and NCCTG N9831 regimens: doxorubicin and cyclophosphamide followed by paclitaxel (AC→T) or paclitaxel plus trastuzumab (AC→TH). | ||||||||
Figure 7 Duration of Overall Survival in Patients from the Joint Analysis: NSABP B- 31 and NCCTG N9831
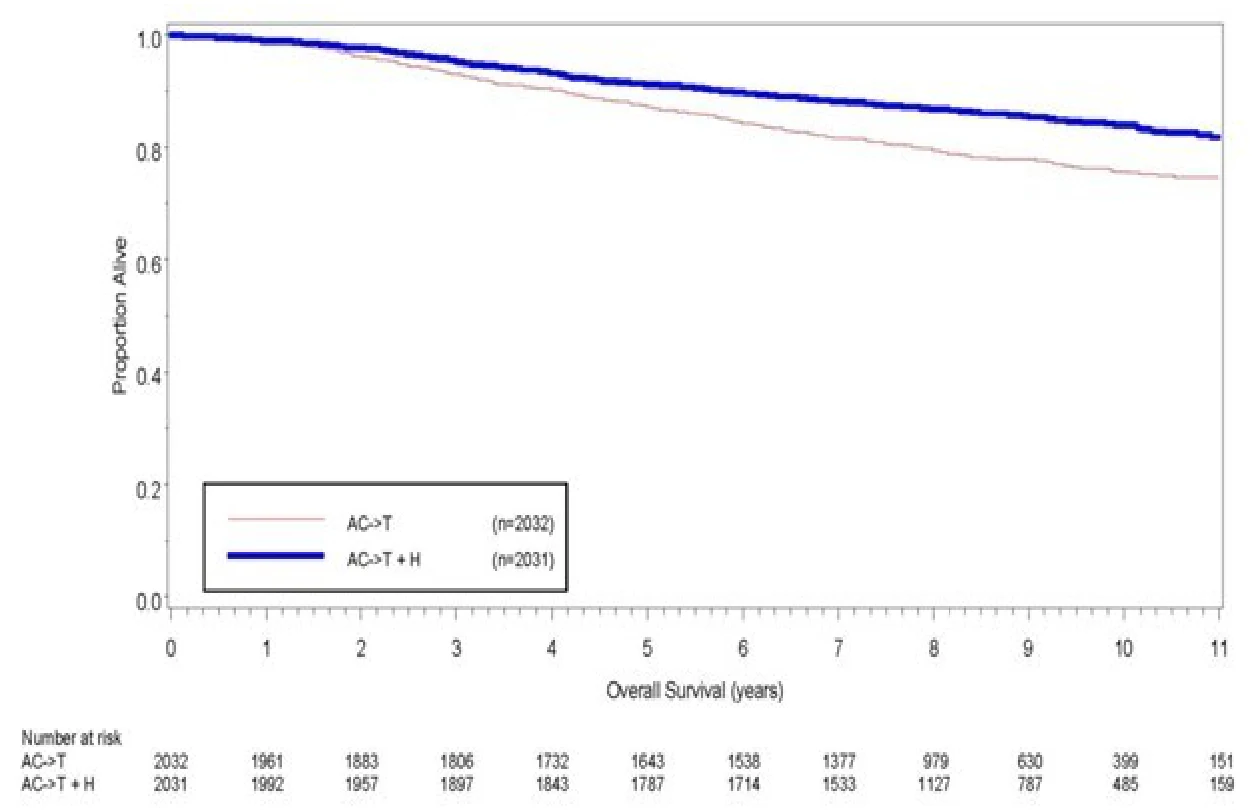
Disease-Free Survival (DFS) analysis was also performed at the final analysis of OS from the joint analysis of studies NSABP B-31 and NCCTG N9831. The updated DFS analysis results showed a similar DFS benefit compared to the definitive primary DFS analysis.
BCIRG-006
In the BCIRG-006 study, patients were randomized (1:1:1) to receive doxorubicin and cyclophosphamide followed by docetaxel (AC→T), doxorubicin and cyclophosphamide followed by docetaxel plus trastuzumab (AC→TH), or docetaxel and carboplatin plus trastuzumab (TCH). Trastuzumab was administered weekly (initial dose of 4 mg/kg followed by weekly dose of 2 mg/kg) concurrently with either T or TC, and then every 3 weeks (6 mg/kg) as monotherapy for a total of 52 weeks.
In the AC→T arm, doxorubicin 60 mg/m2 IV was administered in combination with cyclophosphamide 600 mg/m2 IV on an every 3 week basis for 4 cycles followed by docetaxel 100 mg/m2 as 1 hour IV infusion on an every 3 week basis for 4 cycles.
In the AC→TH arm, every 3 weeks for four cycles, patients in the AC→TH arm received 60 mg/m2 doxorubicin as a 5- to 15-minute intravenous (IV) bolus injection followed by 600 mg/m2 IV cyclophosphamide as a 5- to 60-minute IV bolus injection. Three weeks after the last treatment with AC (i.e., on Day 1 of Cycle 5), a 4-mg/kg trastuzumab loading dose was administered as a 90-minute IV infusion. Beginning on Day 8 of Cycle 5, 2 mg/kg trastuzumab was administered as a 30-minute IV infusion every week. Docetaxel 100 mg/m2 was administered as a 1-hour IV infusion every 3 weeks for four cycles, beginning on Day 2 of Cycle 5 and then on Day 1 of all subsequent cycles. Beginning 3 weeks after the last treatment with docetaxel, 6 mg/kg trastuzumab was administered as a 30-minute IV infusion every 3 weeks.
In the TCH arm, patients received a 4-mg/kg trastuzumab loading dose as a 90-minute IV infusion on Day 1 of Cycle 1. Beginning on Day 8 of Cycle 1, 2 mg/kg trastuzumab was administered as a 30-minute IV infusion every week. Every 3 weeks for six cycles, beginning on Day 2 of Cycle 1 and then on Day 1 of all subsequent cycles, 75 mg/m2 docetaxel was administered as a 1-hour IV infusion, followed by carboplatin at a target area under the concentration–time curve of 6 mg/mL/min as a 30- to 60-minute IV infusion (the dose of carboplatin was calculated using a modified Calvert formula). Beginning 3 weeks after the last treatment with chemotherapy, 6 mg/kg trastuzumab was administered as a 30-minute IV infusion every 3 weeks.
Trastuzumab in combination with docetaxel and carboplatin (TCH) is a non-anthracycline containing regimen and therefore testing of this regimen in study BCIRG-006 offered the possibility to evaluate formally a less cardiotoxic regimen for the adjuvant treatment of early stage HER2 positive breast cancer.
Breast tumour specimens were required to show HER2 gene amplification (FISH+ only) as determined at a central laboratory.
The efficacy results from the BCIRG-006, the primary endpoint of disease-free survival and the secondary endpoint of overall survival, are summarized in the following tables:
Table 36 Overview of Efficacy Analyses BCIRG-006 AC→T versus AC→TH
| Parameter | AC→T (N=1073) | AC→TH (N=1074) | p-value vs AC→T (log-rank) | Hazard Ratio vs AC→T** (95% CI) | |||||
|---|---|---|---|---|---|---|---|---|---|
| Disease-free survival No. patients with event | 195 | 134 | <0.0001 | 0.61 (0.44, 0.85)* | |||||
| Overall survival (Death)*** No. patients with event | 80 | 49 | *** | 0.58 (0.40, 0.83) | |||||
AC→T = doxorubicin plus cyclophosphamide, followed by docetaxel; AC→TH = doxorubicin plus cyclophosphamide, followed by docetaxel plus trastuzumab; CI = confidence interval *The 95% CI is the repeated confidence interval (RCI) adjusted by multiple interim looks. ** Hazard ratio was estimated by Cox regression stratified by number of positive nodes and hormonal receptor status. ***Secondary endpoint | |||||||||
Table 37 Overview of Efficacy Analyses BCIRG-006 AC→T versus TCH
| Parameter | AC→T (N=1073) | TCH (N=1074) | p-value vs AC→T (log-rank) | Hazard Ratio vs AC→T** (95% CI) | ||||
|---|---|---|---|---|---|---|---|---|
| Disease-free survival No. patients with event | 195 | 145 | 0.0003 | 0.67 (0.49,0.92)* | ||||
| Overall survival (Death)*** No. patients with event | 80 | 56 | *** | 0.66 (0.47, 0.93) | ||||
AC→T = doxorubicin plus cyclophosphamide, followed by docetaxel; TCH = docetaxel, carboplatin and trastuzumab; CI = confidence interval *The 95% CI is the repeated confidence interval (RCI) adjusted by multiple interim looks. ** Hazard ratio was estimated by Cox regression stratified by number of positive nodes and hormonal receptor status. ***Secondary endpoint | ||||||||
Figure 8 Duration of Disease-Free Survival in Patients from BCIRG-006
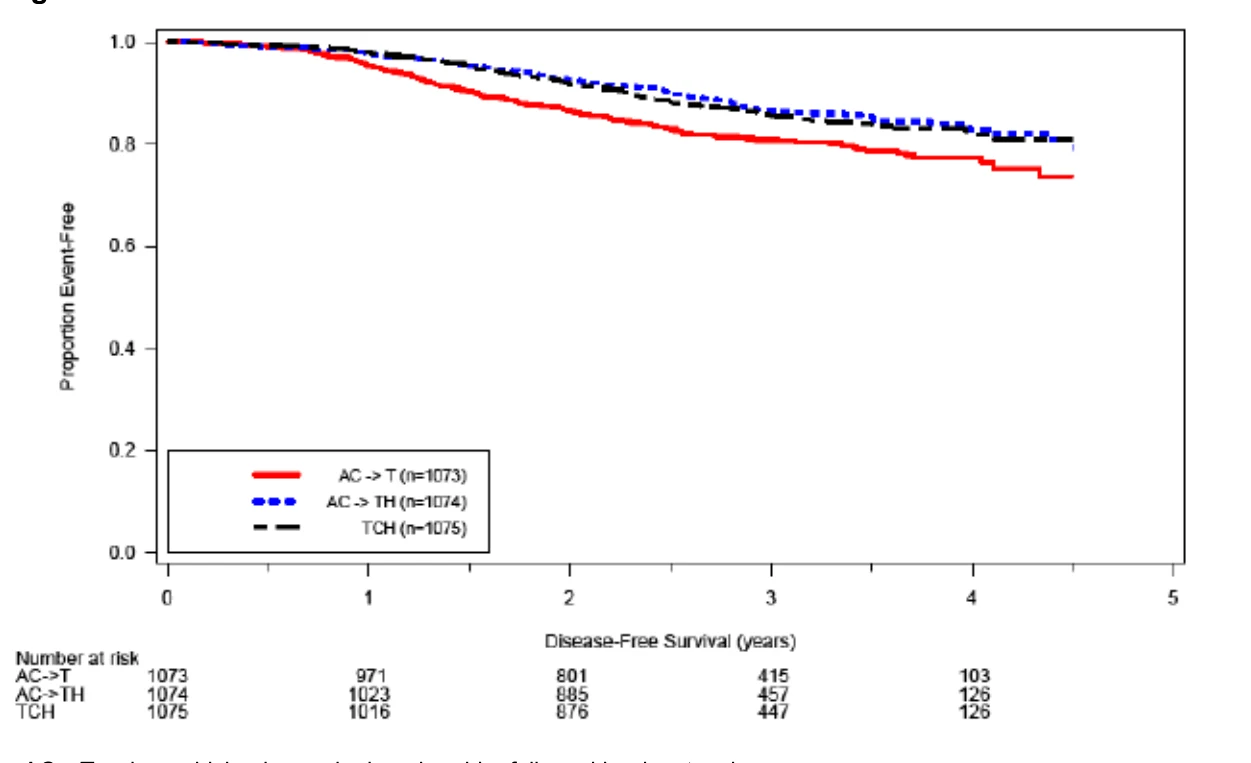
AC→T = doxorubicin plus cyclophosphamide, followed by docetaxel
AC→TH = doxorubicin plus cyclophosphamide, followed by docetaxel plus trastuzumab TCH = docetaxel, carboplatin and trastuzumab
Metastatic Breast Cancer (MBC)
The safety and efficacy of trastuzumab were studied in a multicentre, randomized, controlled clinical trial conducted in 469 patients with HER2- overexpressing MBC who had not been previously treated with chemotherapy for metastatic disease. Patients were eligible if they had 2+ or 3+ levels of overexpression (based on a 0 to 3+ scale) by immunohistochemical assessment of tumour tissue performed by a central testing lab. Eligible patients were randomized to receive chemotherapy alone or in combination with trastuzumab given intravenously as a 4 mg/kg loading dose followed by weekly doses of trastuzumab at 2 mg/kg. For those who had received prior anthracycline therapy in the adjuvant setting, chemotherapy consisted of paclitaxel (175 mg/m2 over 3 hours every 21 days for at least six cycles); for all other patients, chemotherapy consisted of anthracycline plus cyclophosphamide (AC: doxorubicin 60 mg/m2 or epirubicin 75 mg/m2 plus 600 mg/m2 cyclophosphamide every 21 days for six cycles). Compared with patients in the AC subgroups (n=281), patients in the paclitaxel subgroups (n=188) were more likely to have had the following: poor prognostic factors (premenopausal status, estrogen or progesterone receptor negative tumours, positive lymph nodes), prior therapy (adjuvant chemotherapy, myeloablative chemotherapy, radiotherapy), and a shorter disease-free interval.
Compared with patients randomized to chemotherapy alone, the patients randomized to trastuzumab and chemotherapy experienced a significantly longer median time to disease progression, a higher overall response rate (ORR), a longer median duration of response, and a higher one-year survival rate. These treatment effects were observed both in patients who received trastuzumab plus paclitaxel and in those who received trastuzumab plus AC, however the magnitude of the effects was greater in the paclitaxel subgroup. The degree of HER2 overexpression was a predictor of treatment effect.
The results of the study are discussed in Table 38.
Table 38 Phase III Clinical Efficacy in First-Line Treatment
| Combined Results | Paclitaxel Subgroup | AC Subgroup | |||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
trastuzumab + | Chemotherapy | trastuzumab + | Paclitaxel | trastuzumab + | AC | ||||||||||||||||||||||||
| Chemotherapy (n=235) | (n=234) | Paclitaxel (n=92) | (n=96) | ACa (n=143) | (n=138) | ||||||||||||||||||||||||
| Primary Endpoint | |||||||||||||||||||||||||||||
| Time to Progressionb,c | |||||||||||||||||||||||||||||
| Median (months) | 7.6 | 4.6 | 6.9 | 3.0 | 8.1 | 6.1 | |||||||||||||||||||||||
| 95% confidence interval | (7.0, 9.4) | (4.4, 5.4) | (5.3, 9.9) | (2.1, 4.3) | (7.3, 9.9) | (4.9, 7.1) | |||||||||||||||||||||||
| p-value | 0.0001 | 0.0001 | 0.0003 | ||||||||||||||||||||||||||
| Secondary Endpoints | |||||||||||||||||||||||||||||
| Overall Response Rateb | |||||||||||||||||||||||||||||
| Rate (percent) | 48 | 32 | 42 | 16 | 52 | 43 | |||||||||||||||||||||||
| 95% confidence interval | (42, 55) | (26, 38) | (32, 52) | (8, 23) | (44, 61) | (34, 51) | |||||||||||||||||||||||
| p-value | 0.0002 | < 0.0001 | 0.1038 | ||||||||||||||||||||||||||
| Duration of Responseb,c | |||||||||||||||||||||||||||||
| Median (months) | 9.3 | 5.9 | 11.0 | 4.4 | 9.1 | 6.5 | |||||||||||||||||||||||
| 95% confidence interval | (8.0, 11.0) | (5.5, 7.0) | (8.2, >19.8) | (3.9, 5.3) | (7.2, 11.0) | (5.8, 8.0) | |||||||||||||||||||||||
| p-value | 0.0001 | 0.0001 | 0.0025 | ||||||||||||||||||||||||||
| 1-Year Survivalc | |||||||||||||||||||||||||||||
| Percent alive | 78 | 67 | 72 | 60 | 83 | 72 | |||||||||||||||||||||||
| p-value | 0.0080 | 0.0975 | 0.0415 | ||||||||||||||||||||||||||
a AC = anthracycline (doxorubicin or epirubicin) and cyclophosphamide. b Assessed by an independent Response Evaluation Committee. c Kaplan-Meier Estimate | |||||||||||||||||||||||||||||
Trastuzumab was also studied as a single agent in a multicentre, open-label, single-arm clinical trial in patients with HER2- overexpressing metastatic breast cancer who had relapsed following one or two prior chemotherapy regimens for metastatic disease. Of 222 patients enrolled, 68% had received prior adjuvant chemotherapy, 32% had one and 68% had received two prior chemotherapy regimens for metastatic disease, and 26% had received prior myeloablative treatment with hematopoietic rescue. Patients were treated with a loading dose of 4 mg/kg IV followed by weekly doses of trastuzumab at 2 mg/kg. The ORR (complete response + partial response), as determined by an independent Response Evaluation Committee, was 15% (with 8 patients having a complete response and 26 patients with a partial response) with a median survival of 13 months. Complete responses were observed only in patients with disease limited to skin and lymph nodes. The degree of HER2 overexpression was a predictor of treatment effect.
For information on clinical studies with trastuzumab in combination with pertuzumab and docetaxel, consult the Product Monograph for pertuzumab.
Metastatic Gastric Cancer (MGC)
ToGA (BO18255)
Study ToGA (BO18255) was an open-label randomized multicentre, international Phase III study of trastuzumab in combination with a fluoropyrimidine (FP) and cisplatin versus chemotherapy alone in patients with inoperable locally advanced or recurrent and/or metastatic HER2 positive adenocarcinoma of the stomach or gastro-esophageal junction. Eligibility for inclusion required patients to be HER2 positive as determined by either HER2 protein overexpression (IHC) or HER2 gene amplification (FISH), performed by a central laboratory.
At the time of conducting the ToGA (BO18255) trial, the combination of 5-FU or capecitabine and cisplatin was considered to be a standard of care in Canada.
Table 39 Summary of Demographic Data
FP/ Cisplatin (FP) N = 290 | Trastuzumab/ FP/ Cisplatin (H+FP) N = 294 | |
|---|---|---|
| Sex | ||
| Male | 218 (75%) | 226 (77%) |
| Female | 72 (25%) | 68 (23%) |
| Race | ||
| 2 (<1%) | 1 (<1%) | |
| Caucasian | 105 (36%) | 115 (39%) |
| Oriental | 158 (54%) | 151 (51%) |
| Other | 25 (9%) | 27 (9%) |
| Age in years | ||
| Mean | 58.5 | 59.4 |
| SD | 11.22 | 10.75 |
| Median | 59.0 | 61.0 |
| Min-Max | 21-82 | 23-83 |
| Weight in kg | ||
| Mean | 63.17 | 62.08 |
| SD | 13.034 | 12.594 |
| Median | 60.30 | 61.45 |
| Min-Max | 28.0-105.0 | 35.0-110.0 |
| Height in cm | ||
| Mean | 166.4 | 166.3 |
| SD | 8.85 | 8.26 |
| Median | 167.0 | 166.0 |
| Min-Max | 128-190 | 146-198 |
The efficacy results from the ToGA (BO18255) study are summarized in tables 39-41. Patients were recruited to the trial who were previously untreated for HER2 positive inoperable locally advanced or recurrent and/or metastatic adenocarcinoma of the stomach or gastro-oesophageal junction not amenable to curative therapy. The primary endpoint was overall survival which was defined as the time from the date of randomization to the date of death from any cause. At the time of the analysis a total of 349 randomized patients had died: 182 patients (62.8%) in the control arm and 167 patients (56.8%) in the treatment arm. The majority of the deaths were due to events related to the underlying cancer.
The addition of trastuzumab to capecitabine/5-FU and cisplatin resulted in a clinically relevant and statistically significant improvement in the primary endpoint of overall survival (p = 0.0046, Log Rank test). The median survival time was 11.1 months with capecitabine/5-FU and cisplatin and 13.8 months with trastuzumab + capecitabine/5-FU and cisplatin. The risk of death was decreased by 26% (Hazard Ratio [HR] 0.74 95% CI [0.60-0.91]) for patients in the trastuzumab arm compared to the capecitabine/5-FU arm. The results are considered by the study’s independent data monitoring committee as the definitive outcome of the study.
One year after the clinical cutoff date of the definitive efficacy and safety second interim analysis, updated overall survival analysis demonstrated that 446 patients had died: 225 patients (78%) in the control arm and 221 patients (75%) in the treatment arm. The majority of the deaths were due to events related to the underlying cancer. The median survival time was 11.7 months with capecitabine/5-FU and cisplatin and 13.1 months with trastuzumab + capecitabine/5-FU and cisplatin. The risk of death was decreased by 20% (Hazard Ratio [HR] 0.80 repeated CI [0.661,
0.978]) for patients in the trastuzumab arm compared to the capecitabine/5-FU and cisplatin arm (see Table 40 and Figure 9).
Table 40 Summary of Overall Survival Results From Study ToGA (BO18255) Full Analysis Set
| Analysis | Overall Survival, Median months | HR CI*** | p-value | |
|---|---|---|---|---|
FP N = 290 | (H+FP) N = 294 | |||
| 2nd Interim Efficacy and Safety Analysis* | 11.1 | 13.8 | 0.74 (0.573, 0.950) | 0.0046 |
| Updated OS Analysis** | 11.7 | 13.1 | 0.80 (0.661, 0.978) | 0.0215 |
FP: Fluoropyrimidine/cisplatin H+FP: trastuzumab + fluoropyrimidine/cisplatin *The OS results presented in the first row of Table 40 are the results from the second efficacy interim analysis (clinical data cut off date: January 7, 2009). The OS results reviewed by the Independent Data Monitoring Committee (IDMC) from the second interim analysis based on 348 deaths crossed the pre specified statistical boundary of 0.0188 (p=0.0048) and were the definitive outcome of study ToGA (BO18255). **The OS results presented in the second row of Table 40 are the results from the updated OS analysis one year after the clinical cutoff date of the definitive efficacy and safety second interim analysis. *** For the purposes of maintaining confidence intervals at an overall 95% level for the multiple looks at the survival data, repeated confidence intervals (RCIs) for the hazard ratio for OS were calculated. | ||||
Figure 9 Kaplan-Meier Curve for Overall Survival*
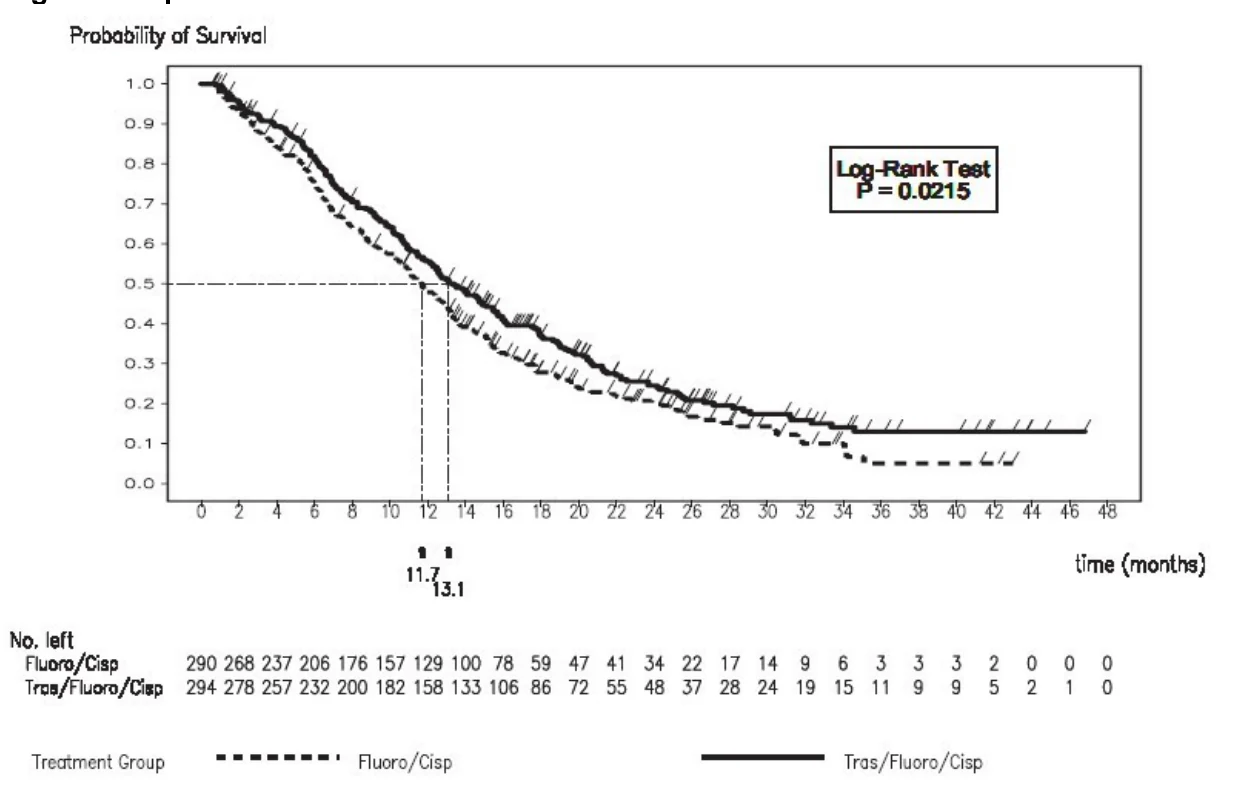
*The Kaplan-Meier curves for the OS are the results from the updated OS analysis one year after the clinical cutoff date of the definitive efficacy and safety second interim analysis.
In trial ToGA (BO18255), post hoc subgroup analyses indicate that a positive treatment effect was limited to tumours with higher levels of HER2 protein (IHC 2+ /FISH+ and IHC 3+). At the time of the second interim efficacy and safety analysis, the median overall survival for the high HER2 expressing group was 11.8 months versus 16 months, HR 0.65 (95% CI 0.51-0.83) (see Table 41).
Table 41 Overall Survival Results by HER2 Status – IHC 0, IHC 1+ versus IHC 3+, IHC 2+/FISH+ (Full Analysis Set)
| Subgroup | FP | H+FP | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Patients per group | N Events | Median time | Patients per group | N Events | Median time | HR | 95% CI for HR | ||||||||
| All | 290 | 182 | 11.1 | 294 | 167 | 13.8 | 0.74 | [0.60; 0.91] | |||||||
HER2 Results | FISH+/IHC 0 or 1+ | 70 | 45 | 8.7 | 61 | 43 | 10.0 | 1.07 | [0.70; 1.62] | ||||||
| FISH- or + or no result/IHC 2+ or 3+ | 218 | 136 | 11.8 | 228 | 120 | 16.0 | 0.65 | [0.51; 0.83] | |||||||
A total of 233 patients [40%] received previous treatments for gastric cancer, which included adjuvant chemotherapy, radiotherapy, and/or surgery: 130 patients [44%] in the FP+H arm and 103 patients [36%] in the FP arm. A total of 351 patients [60%] did not receive previous treatments for gastric cancer. Of these, there were 164 patients [56%] in the FP+H arm and 187 patients [64%] in the FP arm (see Table 42).
Table 42 Analysis Of Overall Survival By Prior Gastric Cancer Treatment: Full Analysis Set
| FP | H+FP | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Patient per Group | Events | Median OS (mo) | Patient per Group | Events | Median OS (mo) | Hazard Ratioa (95% CI) | |||||||||
| All | 290 | 182 | 11.1 | 294 | 167 | 13.8 | 0.74 (0.60, 0.91) | ||||||||
| Prior treatment for gastric cancer | |||||||||||||||
| No | 187 | 123 | 10.2 | 164 | 101 | 12.6 | 0.67 (0.51, 0.88) | ||||||||
| Yes | 103 | 59 | 13.5 | 130 | 66 | 14.6 | 0.88 (0.62, 1.25) | ||||||||
| a Relative to fluoropyrimidine/cisplatin; based on unstratified analysis. | |||||||||||||||
The results for the primary endpoint of the study ToGA (BO18255), overall survival, were supported by the improvements in the secondary efficacy parameters of PFS, time to progression, overall response rate, and duration of response. At the time of the second interim efficacy and safety analysis, for the FP + H arm versus the FP arm, median PFS was 6.7 months versus 5.5 months; median time to progression was 7.1 months versus 5.6 months; overall response rate was 47.3% (139/294) versus 34.5% (100/290); and median duration of response was 6.9 months versus 4.8 months.
18 NON-CLINICAL TOXICOLOGY– REFERENCE BIOLOGIC DRUG
The trastuzumab toxicology program addressed issues of species specificity, chronic administration, coadministration with chemotherapeutic agents, manufacturing process optimization, and changes in formulation.
Trastuzumab is specific for the human p185HER2 receptor and does not bind the corresponding rodent receptor (p185neu). The in vitro tissue binding profile of trastuzumab to monkey tissues demonstrated that the monkey was an appropriate model for comprehensive toxicity testing.
Acute Toxicity Studies: In acute dose studies, trastuzumab was well tolerated and produced no evidence of systemic toxicity at any dose tested, including the highest dose that could be delivered of a 5 mg/mL formulation. Intravenous administration of trastuzumab as a single dose of 94 mg/kg (mice), or 47-50 mg/kg (monkeys), produced no findings of toxicologic significance in any parameter evaluated.
Bridging studies conducted in monkeys to evaluate the safety and pharmacokinetics of trastuzumab, produced by optimization of the manufacturing process including a cell line change (from H2 to H13), revealed no evidence of acute toxicity or changes in pharmacokinetic disposition in monkeys. Trastuzumab produced from a subsequent manufacturing scale up and formulation change (lyophilization) resulted in comparable pharmacokinetic profiles in monkeys and had no effect on safety endpoints.
The findings from the acute toxicity studies with trastuzumab are summarized in Table 43.
Multidose Toxicity Studies: In multiple-dose studies, trastuzumab was well tolerated and produced no evidence of systemic toxicity at any dose tested, including the highest dose that could be delivered of 25 mg/kg. Intravenous administration of trastuzumab as multiple intravenous doses in monkeys of up to 25 mg/kg given weekly for 26 weeks, or twice-weekly for up to 12 weeks, produced no findings of toxicologic significance in any parameter evaluated.
Some isolated changes in ECG, which followed no apparent pattern, were observed in the multiple intravenous doses study in monkeys, dosed up to 25 mg/kg weekly for 26 weeks. The following is a summary of the electrocardiographic findings that were statistically significant in this study from control. In female monkeys, at weeks 5 and 21, the Q-T interval for the 5 mg/kg dose was 0.22 seconds (Vehicle 0.18 seconds) and for the 25 mg/kg dose was 0.23 seconds (Vehicle 0.18 seconds). In male monkeys, at weeks 9 and 17, the Q-T interval for the 1 mg/kg dose was 0.16 seconds (Vehicle 0.21 seconds) and for the 25 mg/kg dose was 0.04 seconds (Vehicle 0.03 seconds). The heart rate, at week 17, for the 5 and 25 mg/kg dose, was 145 and 160 beats/minute, respectively (Vehicle 183 beats/minute). There were no statistically significant electrocardiographic findings in female monkeys at weeks 9, 13, 17 and 26, and in male monkeys at weeks 5, 13, 21 and 26. In male monkeys during the recovery phase (weeks 30 and 34), the heart rate for the 25 mg/kg dose was 190 beats/minute (Vehicle 160 beats/minute) and 180 beats/minute (Vehicle 200 beats/minute), respectively; while the Q-T interval was 0.19 seconds (Vehicle 0.22 seconds) and 0.23 seconds (Vehicle 0.19 seconds), respectively. In female monkeys, at weeks 30 and 34, the heart rate was 190 beats/minute (Vehicle 210 beats/minute) and 140 beats/minute (Vehicle 180 beats/minute), respectively; while the Q-T interval was 0.22 seconds (Vehicle 0.17 seconds) and 0.26 seconds (Vehicle 0.21 seconds), respectively for the 25 mg/kg dose.
Although, administration of trastuzumab was associated with a mild reduction in heart rate in some male monkeys receiving 5 or 25 mg/kg, this was not considered toxicologically significant since bradycardia was not present in these monkeys. There was no toxicological significance of the aberrant ventricular complexes seen in monkeys treated with trastuzumab since these were not seen broadly in all treated monkeys. Occasional abnormal complexes may be observed in normal animals.
The findings from the multidose toxicity studies with trastuzumab are summarized in Table 44.
Special Toxicity Studies: Specific toxicity studies performed with trastuzumab included: issue cross-reactivity studies in human and monkey tissue, immunogenicity, drug interaction, and local tolerance studies, in vitro hemolytic potential/blood compatibility studies, and a systemic toxicity study in mice with the formulation component trehalose. Details from these studies are provided in Table 45.
No gross or histopathologic changes were observed in tissues which demonstrated trastuzumab binding in the tissue cross-reactivity studies.
In addition, trehalose, a component of the lyophilized formulation, produced no evidence of clinical or anatomical toxicity when given daily to mice at intravenous doses of up to 1 g/kg. Single dose drug interaction studies in which 1.5 mg/kg trastuzumab (lower than the recommended dose) was administered intravenously with single doses of doxorubicin, cyclophosphamide, paclitaxel, or the combination of doxorubicin and cyclophosphamide, did not show any significant alterations in disposition profiles of trastuzumab, or any of the chemotherapeutic agents, that might suggest possible safety or efficacy concerns. In local tolerance studies conducted in rabbits, no gross or histopathologic evidence of irritative potential was noted following intravenous administration of the liquid or lyophilized trastuzumab formulations at a concentration of 5 mg/mL. Both the liquid and lyophilized formulations are compatible with whole blood, serum, and plasma obtained from humans and monkeys.
Table 43 Overall Summary of Nonclinical Acute Toxicity Studies with Trastuzumab
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Lot No. | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | ||||||||
| 91-629-1450 | Acute Single Dose (GLP) | Mouse/Crl: CD-1® (ICR) BR/VAF/PlusTM | 5/M 5/F | IV | 0 9.4 47 94 | M3-RD175 | --- 4.7x NA 47x | --- 2.8x NA 19x | At least 2 weeks |
| Comments: Trastuzumab was well tolerated and the no observable effect level (NOEL) after a single intravenous bolus injection of trastuzumab was 94.0 mg/kg in mice. | |||||||||
| 91-640-1450 | Acute Single Dose (GLP) | Monkey/Rhesus | 2/M 2/F | IV | 0 4.7 23.5 47 | M3-RD175 | --- 2.4x NA 24x | --- 1x NA 12x | At least 2 weeks |
| Comments: Trastuzumab was well tolerated and the no observable effect level (NOEL) after a single intravenous bolus injection of trastuzumab was 47.0 mg/kg in rhesus monkeys. | |||||||||
| 94-173-1450a | Acute Single Dose (GLP) | Monkey/Rhesus | 2/M 2/F | IV | 0 5 50 50 | M3-RD319 A9806AX | ---- 2.5x 2.5x 2.5x | ---- NA NA NA | At least 2 weeks |
| Comments: A single intravenous dose of trastuzumab H13 or trastuzumab H2 up to 50 mg/kg was well tolerated and produced no adverse effects in rhesus monkeys. | |||||||||
| 94-436-1450b | Acute Single Dose (GLP) | Monkey/Rhesus | 4F | IV | 1.5 1.5 | M3-RD319 C9802AX | 0.8x 0.8x | NA NA | 30 days |
| Comments: The single intravenous administration of trastuzumab (H13-1K) or trastuzumab (H13-12K) at a dose level of 1.5 mg/kg was well tolerated and produced no test material-related differential effects on toxicity parameters in female rhesus monkeys. | |||||||||
| 95-490-1450c | Acute Single Dose (GLP) | Monkey/Rhesus | 6/F | IV | 1.5 1.5 | M4-RD494 C9807AX | 0.8x 0.8x | NA NA | 11 weeks |
| Comments: This crossover study was conducted to provide serum samples from rhesus monkeys following single intravenous bolus injections of trastuzumab (single dose liquid formulation) and trastuzumab (multi-dose lyophilized formulation) to compare their pharmacokinetic profiles. All animals survived the study, and no test material-related overt clinical signs of toxicity were observed. Furthermore, there were no statistically significant or otherwise notable differences between the two groups that might be attributed to the different formulations. | |||||||||
IV=Intravenous a This study was conducted to support a liquid formulation process change from trastuzumab H2 to trastuzumab H13. b This study was conducted to support the clinical use of trastuzumab produced by a scaled-up manufacturing process, trastuzumab (H13-12K) c This study was conducted to support the clinical use of lyophilized trastuzumab. | |||||||||
Table 44 Overall Summary of Nonclinical Multidose Toxicity Studies with Trastuzumab
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | |||||||
| 91-667-1450 | Multidose (GLP) | Monkey/ Rhesus | 4-6/M 4-6/F | IV | 0 2.35 11.75 23.5 | --- 2.4x 12x 24x | --- 2x 11x 21x | 8 weeks |
| Comments: Intravenous bolus injections of trastuzumab at doses of up to 23.5 mg/kg were well tolerated when administered twice weekly for approximately 4 weeks. | ||||||||
| 94-455-1450 | Multidose (GLP) | Monkey/ Cynomolgus | 4-6/M 4-6/F | IV | 0 1 5 25 | --- 0.5x 2.5x 13x | --- 0.3x 3x 14x | 8 months |
| Comments: Intravenous bolus injections of trastuzumab up to 25 mg/kg were well-tolerated and produce no evidence of toxicity when administered to cynomolgus monkeys once a week for approximately 6 months. However, some changes in ECG were noted at various times (Refer to the TOXICOLOGY - Multidose Toxicity Studies discussion section. | ||||||||
| 97-333-1450 | Multidose (GLP) | Monkey/ Cynomolgus | 4-6/M 4-6/F | IV | 0 1 5 25 | --- 1x 5x 25x | --- NA NA NA | 5 months |
| Comments: Based on preliminary evaluation of the results of this study, administration of trastuzumab produced no apparent adverse effects on male or female cynomologus monkeys at doses up to 25 mg/kg. | ||||||||
| IV=Intravenous, NA=not available | ||||||||
Table 45 Overall Summary of Nonclinical Special Toxicity Studies with Trastuzumab
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | |||||||
| 91-663-1450 | Tissue Cross-Reactivity (GLP) | Human Tissue | NA | NA | 2.5 µg/mL 50 µg/mL | 0.02xa 0.04xa | NA NA | NA |
| Comments: Humanized antibody trastuzumab defects an antigen that has a restricted distribution in epithelial cells and carcinomas. Murine antibody muMab 4D5 reacts in normal tissues paralleling the patterns observed for trastuzumab. Differences in staining may reflect methodological conditions employed to detect these two antibodies. The patterns of immunoreactivities observed in human tumours are almost identical for these two antibodies. | ||||||||
| 91-686-1450 | Tissue Cross-Reactivity (GLP) | Monkey/Rhesus Tissue | NA | NA | 2.5 µg/mL 0.79 µg/mL | 20xa 6xa | NA NA | NA |
| Comments: muMab 4D5 detected an antigen in nerve and epithelial cells of various normal tissues. The pattern of staining observed with humanized trastuzumab was similar in distribution, but inconsistent and less intense. The differences in staining observed between trastuzumab and muMab 4D5 may be attributed to methodological differences in detection of the two antibodies. The results indicated that rhesus monkey expresses an antigen which is recognized by monoclonal antibodies to p185HER2. | ||||||||
| 92-458-1450b | Multidose Immunogenicity (GLP) | Monkey/ Cynomolgus | 3/F | IV | 5.0 5.0 5.0 5.0 | 2.5x 2.5x 2.5x 2.5x | 2.9x 2.5x 1.9x 1.0x | 6 months |
| Comments: Weekly administration of 5.0 mg/mL of the test material, trastuzumab (high glutamine variant), trastuzumab (low glutamine variant) and trastuzumab (arginine variant) or muMab 4D5 in cynomologus monkeys was well tolerated. Trastuzumab, trastuzumab (high glutamine variant), trastuzumab (low glutamine variant), and trastuzumab (arginine variant) were not immunogenic based on expected pharmacokinetics and a lack of antibody response, whereas muMab 4D5 was considered immunogenic in the cynomolgus monkey. | ||||||||
| 93-446-1450c | Follow-Up Immunogenicity (GLP) | Monkey/ Cynomolgus | 3/F | IV | 5.0 5.0 | 2.5x 2.5x | NA NA | 2 weeks |
| Comments: An intravenous challenge dose of 5.0 mg/kg of trastuzumab (high glutamine variant) or trastuzumab (low glutamine variant) was well tolerated and was not immunogenic as measured by antibody formation in female cynomolgus monkeys. | ||||||||
| 94-241-1450 | Single-Dose Drug Interaction (GLP) | Monkey/Rhesus | 3/F | IV | 1.5 | 0.8x | NA | 3weeks |
| Comments: A single intravenous injection of trastuzumab liquid formulation (at doses that approximate the human clinical dose on a body weight basis), when given alone or in combination with Adriamycin® or Taxol®, or when given in combination of Adriamycin® or Cytoxan®, was well tolerated and produced no evidence of systemic toxicity. | ||||||||
| 91-639-1450 | Acute Local Tolerance (GLP) | Rabbit/Hra: (NZW) SPF | 9/F | IV | 0 1.9 | --- 1x | --- NA | 7 days |
| Comments: The test material and excipient formulations are not considered to be locally irritating following a single bolus intravenous administration in rabbits. | ||||||||
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | |||||||
| 95-502-1450 | Acute Local Torerance (GLP) | Rabbit/Hra: (NZW) SPF | IV IV SC SC | 0 5 mg/mL 50 mg/mL 100 mg/mL | --- 1x 9.5x 19x | --- NA NA NA | 7 days | |
| Comments: Administration of trastuzumab given as a single intravenous bolus injection following reconstitution with 1.1% benzyl alcohol and dilution with saline to a concentration of 5 mg/mL, or given as a single subcutaneous injection following reconstitution with 1.1% benzyl alcohol to a concentration of 100 mg/mL, or dilution with saline to 50 mg/mL is well-tolerated in rabbits and produces no evidence of local irritation attributable to the test material. | ||||||||
| 91-668-1450 | Hemolytic Potential Blood Compatibility (GLP) | Monkey/Rhesus and Human blood and plasma | NA | NA | 4.7 mg/mL | 38xa | NA | NA |
| Comments: Trastuzumab (at a concentration of 4.7 mg/mL) and excipient trastuzumab did not cause hemolysis of human or rhesus monkey erythrocytes and were compatible with human and rhesus monkey serum and plasma. | ||||||||
| 95-501-1450 | Hemolytic Potential Blood Compatibility (GLP) | Monkey/Rhesus and Human blood and plasma | NA | NA | 5 mg/mL | 41xa | NA | NA |
| Comments: Trastuzumab (at a concentration of 5 mg/mL) and trastuzumab vehicle (diluted to a concentration equivalent to a 5 mg/mL trastuzumab concentration) did not cause hemolysis of rhesus monkey or human erythrocytes and are compatible with rhesus monkey and human serum and plasma. | ||||||||
| 96-014-1450 | Multidose (GLP) with Trehalose | Mouse/Crl: CD1® (ICR)BRVAF/Plus® | 10/M 10/F | IV | 0 10 100 1000 | --- 35xd 350xd 3500xd | - NA NA NA | 2 weeks |
| Comments: Daily intravenous administration of trehalose for 2 weeks was well tolerated and produced no adverse effects at doses up to and including 1000 mg/kg in male and female mice. | ||||||||
IV=Intravenous, NA=not available, SC=Subcutaneous, IP=Intraperitoneal Adriamycin is a registered Trade-Mark of Pharmacia & Upjohn S.P.A. Taxol is a registered Trade-Mark of Bristol-Myers Squibb Company Cytoxan is a registered Trade-Mark of Mead Johnson & Company | ||||||||
a Animals were not dosed so AUC ratios cannot be calculated, however the ratio of concentration applied in vitro to tissues/maximum average concentration observed in human circulation (123 μg/mL) is presented here. b The immunogenic potential to two trastuzumab (H2) preparations, containing high or low levels of glutamine variant, and an arginine variant-containing trastuzumab preparation, was compared to the immunogenic potential of the murine counterpart antibody, muMAb 4D5. c This study was conducted to further assess the immunogenic potential of the presence of glutamine variant in trastuzumab (H2). A single challenge dose was administered to those monkeys (in Study 92-458-1450) that had received 6 months of weekly injections of the high or low glutamine variant-containing trastuzumab (H2) preparations. d The ratio of trehalose dose/projected final trastuzumab formulation trehalose dose (~2 mg/kg) is presented here. ® registered Trade-Marks of their respective owners. | ||||||||
Reproductive Toxicity: The results of reproductive toxicity studies conducted in female cynomolgus monkeys given trastuzumab as daily intravenous injections for 4 days followed by twice-weekly administration for the duration of the dosing period revealed no alterations in menstrual cyclicity or sex hormone profiles, and no trastuzumab-related embryotoxicity or effects on fetal development. Pregnancy did not appear to affect maternal exposure to trastuzumab.
When trastuzumab was administered during the period of organogenesis, fetal serum trastuzumab concentrations ranged from 10%-19% of maternal values. Administration during the last trimester was associated with trastuzumab fetal serum concentrations of approximately 33% of maternal concentrations. The difference in fetal serum trastuzumab concentrations obtained in the early and late gestational periods may be attributable to the time between trastuzumab administration and maternal/fetal blood sampling (e.g., samples were obtained 50 days, early gestational study, or 2 days, late gestational study, after the final trastuzumab administration). However, an increase in fetal/maternal serum concentration ratio is consistent with an increase in immunoglobulin transfer rate observed as gestation progresses in both humans and in nonhuman primates. Compared to serum concentrations, trastuzumab was detected at relatively low levels in the milk of lactating monkeys. Trastuzumab detected in the milk of lactating monkeys had no effect on neonatal growth and development from birth to one month of age when study was terminated. A summary of the reproduction studies conducted with trastuzumab is provided in Table 46.
Carcinogenicity: Trastuzumab has not been tested for its carcinogenic potential.
Mutagenicity: Trastuzumab has not been associated with any evidence of mutagenic potential in a mouse micronucleus test, a bacterial mutation test, or in a chromosomal aberration assay in human lymphocytes. These studies are summarized in Table 47.
Table 46 Overall Summary of Nonclinical Reproduction Studies with Trastuzumab
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | |||||||
| 95-038-1450 | Fertility valuation (GLP) | Monkey/Cynomolgus | 6/F | IV | 0 1 5 25 | --- 1x 5x 25x | --- 8.0xa 2.2xa 1.6x+ | 7 Menstrual Cycles |
| Comments: Intravenous administration of trastuzumab at dose levels of 1, 5, and 25 mg/kg during three menstrual cycles was not associated with signs of toxicity, alterations in menstrual cyclicity, or in sex hormone profiles. | ||||||||
| 95-039-1450 | Embryo-Fetal Development (GLP) | Monkey/Cynomolgus | 12/F | IV | 0 1 5 25 | --- 1x 5x 25x | --- 7.2xa 2.2xa 1.8xa | 100 days |
| Comments: Intravenous administration of trastuzumab at doses of 1, 5, and 25 mg/kg on Days 20, 21, 22, 23, 27, 30, 34, 37, 41, 44, 47, and 50 of gestation was well tolerated and did not elicit maternal toxicity, embryotoxicity, or teratogenicity. However, five maternal deaths occurred in this study. Two pregnant monkeys, one in the 1.0 mg/kg group and one in the vehicle control group, died without delivery or abortion and were therefore replaced. Three subsequent maternal deaths, two in the 1.0 mg/kg dose group and one in the 25 mg/kg dose group, occurred following abortion of the fetus. The deaths were attributed to the presence of a retroviral infection within the animal colony and not to administration of trastuzumab. | ||||||||
| 95-238-1450 | Late Gestation Placental Transfer (GLP) | Monkey/Cynomolgus | 8/F | IV | 25 | 25x | 1.7x | 7 months |
| Comments: Administration of trastuzumab at an intravenous bolus dose of 25 mg/kg during the period of late gestation and lactation did not elicit maternal, fetal, or neonatal toxicity. | ||||||||
IV=intravenous * Sparse pharmacokinetic sampling precludes direct calculation of AUC ratios, however, the ratio of dose-adjusted steady-state trough concentrations of animal/human are presented here. | ||||||||
Table 47 Overall Summary of Nonclinical Mutagenicity Studies with Trastuzumab
| Study No. | Study Type | Species/Strain | No./Sex/Group | Route of Admin. | Dose (mg/kg) | Estimated Safety Factor | Study Duration | |
|---|---|---|---|---|---|---|---|---|
| Body Weight Ratio | AUCA/AUCH | |||||||
| 98-024-1450 | In Vivo Micronucleus (GLP) | Mouse/ICR/ (CRj: CD-1,SPF) | 6/M | IV | 0 29.5 59 118 | --- 15x 30x 59x | --- NA NA NA | 24 hours |
| Comments: Trastuzumab was found to be negative for causing clastogenic damage as measured by micronucleus induction for the bone marrow cells of male ICR mice. | ||||||||
| 94-382-1450 | Mutagenicity (GLP) | Salmonella typhimurium E. coli | NA | NA | 0-5000 μg/mL | --- 41xa | --- NA | NA |
| Comments: Trastuzumab was unable to induce mutation in 4 strains of Salmonella typhimurium and 2 strains of E. coli, when tested at concentrations up to 5000 μg/mL in the absence of a rat liver metabolic activation system (S-9), and 3750 μg/mL in its presence, with treatments performed using a “treat and plate” protocol. All trastuzumab treatments of the test strains, both in the absence and in the presence of S-9, failed to produce a statistically significant increase in revertant numbers when the data were analysed at the 1% level using Dunnett’s test. This study was therefore considered to have provided no evidence of trastuzumab mutagenic activity. | ||||||||
| 97-101-1450 | Cytogenicity (GLP) | Human Lymphocytes | NA | NA | 0-5000 μg/mL | --- 41xa | --- NA | NA |
| Comments: Trastuzumab was considered negative for inducing chromosomal aberrations in human whole blood lymphocytes when treated with trastuzumab at doses up to and including 5000 μg/mL with and without metabolic activation. These results were verified in independently conducted confirmatory trials. | ||||||||
IV=intravenous, NA=not applicable. * Animals were not dosed so AUC ratios cannot be calculated, however the ratio of concentration examined in vitro/maximum average concentration observed in human circulation (123 μg/mL) is presented here. | ||||||||
19 SUPPORTING PRODUCT MONOGRAPHS
HERCEPTIN® (Intravenous Infusion, 440mg/vial), submission control 235646, Product Monograph, Hoffmann-La Roche Ltd. (May 7, 2020)