


Product Monograph - Ifosfamide for Injection
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Intravenous | Powder for Solution / 1 g / vial and 3 g / vial | There are no nonmedicinal ingredients. |
INDICATIONS AND CLINICAL USE
Ifosfamide for Injection is indicated as follows:
Soft Tissue Sarcoma
- first-line single agent therapy;
- second-line single agent therapy in patients who have failed to respond or who have relapsed on other chemotherapeutic regimens.
Pancreatic Carcinoma
- second-line single agent therapy in patients who have failed to respond or who have relapsed on other chemotherapeutic regimens.
Cervical Carcinoma
- as a single agent or in combination with Cisplatin and Bleomycin in advanced or recurrent disease.
Ifosfamide for Injection is a potent drug and should only be administered by a qualified healthcare professional experienced in the use of antineoplastic therapy (See WARNINGS AND PRECAUTIONS).
Geriatrics (> 65 years of age): In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Pediatrics (<16 years of age): Although Ifosfamide for Injection is used in pediatric patients, its safety and efficacy have not been formally assessed in a registration trial.
CONTRAINDICATIONS
Ifosfamide for Injection – Product Monograph
Ifosfamide for Injection is contraindicated in patients with:
- a known hypersensitivity to it
- severe myelosuppression
- severe renal impairment
- severe hepatic impairment
- an active infection (bacterial, fungal, viral)/severe immunosuppression
- urinary tract disease (cystitis, obstructions to the urine flow)
- advanced cerebral arteriosclerosis
See also WARNINGS AND PRECAUTIONS.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
Ifosfamide should be given cautiously to patients with any of the following conditions:
- Prior radiotherapy,
- Prior therapy with other cytotoxic agents,
- Extensive bone marrow metastases,
- Brain metastases,
- Reduced nephron reserve,
- Impaired renal function,
- Hepatic impairment.
Ifosfamide for Injection – Product Monograph
Prior to initiating treatment, it is necessary to exclude or correct any electrolyte imbalances.
The cytotoxic effect of ifosfamide occurs after its activation, which takes place mainly in the liver. Therefore, the risk of tissue injury from accidental paravenous administration is low. In case of accidental paravenous administration of ifosfamide, the infusion should be stopped immediately, the extravascular ifosfamide solution should be aspirated with the cannula in place, and other measures should be instituted as appropriate.
Carcinogenesis and Mutagenesis
Treatment with ifosfamide involves the risk of secondary tumors and their precursors as late sequelae. Ifosfamide, like other alkylating agents, has been reported to have oncogenic activity in animals. Thus the possibility that it may have oncogenic potential in humans should be considered.
The risk of myelodysplastic alterations, some progressing to acute leukemias, is increased. Other malignancies reported after use of ifosfamide or regimens with ifosfamide include lymphoma, thyroid cancer, and sarcomas. The secondary malignancy may develop several years after chemotherapy has been discontinued.
Malignancy has also been reported after in utero exposure with cyclophosphamide, another oxazaphosphorine cytotoxic agent.
Cardiovascular
Ifosfamide should be given cautiously to patients with risk factors for cardiotoxicity and patients with pre-existing cardiac disease.
Manifestations of cardiotoxicity reported with ifosfamide treatment include:
- Supraventricular or ventricular arrhythmias, including atrial/ supraventricular tachycardia, atrial fibrillation, pulseless ventricular tachycardia;
- Decreased QRS voltage and ST-segment or T-wave changes;
- Toxic cardiomyopathy leading to heart failure with congestion and hypotension;
- Pericardial effusion, fibrinous pericarditis, and epicardial fibrosis.
Fatal outcome of ifosfamide-associated cardiotoxicity has been reported.
The risk of developing cardiotoxic effects is dose-dependent. It is increased in patients with prior or concomitant treatment with other cardiotoxic agents or radiation of the cardiac region and, possibly, renal impairment.
Gastrointestinal
Ifosfamide very commonly causes nausea and vomiting. Antiemetics for prevention and amelioration of nausea and vomiting should be used. Alcohol consumption may increase the severity of chemotherapy-induced nausea and vomiting.
Administration of ifosfamide may cause stomatitis (oral mucositis). Current guidelines on measures for prevention and amelioration of stomatitis should be considered.
Ifosfamide for Injection – Product Monograph
Genitourinary
Ifosfamide is urotoxic. Urotoxic side effects, especially hemorrhagic cystitis, have been frequently associated with the use of ifosfamide. Hemorrhagic cystitis after a single dose of ifosfamide has been reported. Manifestations of urotoxicity include hemorrhagic cystitis (including severe forms with ulceration and necrosis), hematuria, which may be severe, signs of urothelial irritation (such as painful micturition, a feeling of residual urine, frequent voiding, nocturia, urinary incontinence) as well as the development of bladder fibrosis, small-capacity bladder, telangiectasia, recurrent hematuria and signs of chronic bladder irritation. The risk of hemorrhagic cystitis is dose-dependent and increased with administration of single high doses compared to fractionated administration. Past or concomitant radiation of the bladder or busulfan treatment may increase the risk for hemorrhagic cystitis.
Pyelitis and ureteritis have been reported with cyclophosphamide, another oxazaphosphorine cytotoxic agent.
Hemorrhagic cystitis requiring blood transfusion has been reported with ifosfamide. Fatal outcome of urothelial toxicity, as well as the need for cystectomy due to fibrosis, bleeding, or secondary malignancy has been reported with cyclophosphamide, another oxazaphosphorine cytotoxic agent.
Experience with cyclophosphamide, another oxazaphosphorine cytotoxic agent shows that, while hematuria usually resolves in a few days after treatment is stopped, it may persist.
The therapeutic benefit of mesna as an uroprotective agent has been demonstrated in that the incidence of urinary tract complications was reduced from 40% to 3.5%. Thus ifosfamide should always be accompanied by uroprotective treatment with mesna.
It is recommended that a urine analysis should be obtained prior to each dose of ifosfamide. Any obstruction of the efferent urinary tract and cystitis as well as infections and electrolyte imbalances must be ruled out or eliminated before start of therapy.
Urinary sediment should be examined at regular intervals.
Adequate amounts of fluid should be ingested or infused to force diuresis in order to reduce the risk of urinary tract toxicity (see DOSAGE AND ADMINISTRATION).
Active urinary tract infections are a contraindication to the use of ifosfamide.
The following adverse reactions have been reported with another oxazaphosphorine cytostatic agent: renal pelvis cancer, ureteric cancer, bladder cancer, bladder necrosis, bladder fibrosis, bladder contracture, hemorrhagic pyelitis, hemorrhagic ureteritis, ulcerative cystitis.
Hematologic
Ifosfamide should be given cautiously to patients with any of the following conditions:
- Leukopenia,
- Thrombocytopenia,
- Tumour-cell infiltration of the bone marrow,
- Impairment of bone marrow function.
Ifosfamide for Injection – Product Monograph
Severe myelosuppression must be expected particularly in patients pretreated with and/or receiving concomitant chemotherapy/hematotoxic agents and/or radiation therapy. Concomitant use of other immunosuppressants may increase immunosupression induced by ifosfamide. See DRUG INTERACTIONS. The risk of myelosuppression is dose-dependent and is increased with administration of a single high dose compared to fractionated administration. The risk of myelosuppression is increased in patients with reduced renal function.
Ifosfamide may cause myelosuppression and significant hematologic toxicities which may prove fatal despite careful monitoring prior to and during therapy. Ifosfamide-induced myelosuppression can cause leukopenia, neutropenia, thrombocytopenia (associated with a higher risk of bleeding events), and anemia.
Close hematologic monitoring is recommended. Leukocyte, erythrocyte and platelet counts should be carried out prior to each administration and at regular intervals. There is normally a reduction in the leukocyte count beginning on approximately day 5. The nadir, depending on dosage and baseline count, tends to be reached after 8 - 10 days. Recovery occurs after 10 - 14 days and is usually complete after 2 - 3 weeks.
Hepatic/Biliary/Pancreatic
Ifosfamide should be given cautiously to patients with the following conditions:
- Impaired hepatic function
- Abnormal serum albumin levels
Hepatic impairment, particularly if severe, may be associated with decreased activation of ifosfamide. This may alter the effectiveness of ifosfamide treatment. Low serum albumin and hepatic impairment are also considered risk factors for the development of CNS toxicity. Hepatic impairment may increase the formation of a metabolite that is believed to cause or contribute to CNS toxicity and also contribute to nephrotoxicity. This should be considered when selecting the dose and interpreting response to the dose selected.
Veno-occlusive liver disease has been reported with chemotherapy that included ifosfamide.
Immune
Ifosfamide is contraindicated in patients with the following conditions:
- Presence of known infections
- Severe immunosuppression (see CONTRAINDICATIONS)
Prior to initiating treatment, it is necessary to exclude or correct any infections.
Because ifosfamide may exert a suppressive action in immune mechanisms, treatment with Ifosfamide should be interrupted for patients who develop bacterial, fungal or viral infections. This is especially true for patients receiving concomitant steroid therapy, since infections in some of these patients have been fatal.
Severe immunosuppression has led to serious, sometimes fatal, infections. Sepsis and septic
Ifosfamide for Injection – Product Monograph
shock have also been reported. Infections reported with ifosfamide include pneumonias, as well as other bacterial, fungal, viral, and parasitic infections.
Latent infections can be reactivated. In patients treated with ifosfamide, reactivation has been reported for various viral infections.
Neurologic
Ifosfamide may cause significant neurologic toxicities which may prove fatal despite careful monitoring prior to and during therapy.
CNS toxicity has been reported very commonly and appears to be dose-dependent.
Careful monitoring is required, in particular for patients with cerebral metastases and others at increased risk, as ifosfamide has been associated with several CNS symptoms.
Neurologic manifestations consisting of somnolence, confusion, hallucinations, coma, blurred vision, psychotic behaviour, extrapyramidal symptoms, urinary incontinence or seizures have been reported with ifosfamide therapy. There also have been reports of peripheral neuropathy associated with ifosfamide use. In the case of ifosfamide- induced CNS symptoms, drugs acting on the CNS (e.g., neuroleptics, selective serotonin-reuptake inhibitors, tricyclic antidepressants, antiemetics, sedatives, narcotics or antihistamines) should be discontinued, if possible, or used with caution. The occurrence of these symptoms requires discontinuing ifosfamide therapy. These symptoms have usually been reversible and supporting therapy should be maintained until their resolution. Occasionally recovery has been incomplete.
Ifosfamide neurotoxicity may become manifest within a few hours to a few days after first administration and in most cases resolves within 48 to 72 hours of ifosfamide discontinuation. Symptoms may persist for longer periods of time.
Recurrence of CNS toxicity after several uneventful treatment courses has been reported.
Neurotoxicity often manifests in patients without identifiable risk factors.
If encephalopathy develops, administration of ifosfamide should be discontinued. The possibility to reintroduce ifosfamide should be determined by the physician after careful assessment of the benefits and risks for the individual patient. Past occurrence of encephalopathy during treatment with ifosfamide has the potential to make the benefit to risk profile of retreatment with ifosfamide less favourable.
Manifestations of CNS toxicity may impair a patient’s ability to operate an automobile or other heavy machinery.
In addition, other risk factors that have been demonstrated or discussed in the literature to cause CNS toxicity include:
- Renal dysfunction, elevated serum creatinine;
Ifosfamide for Injection – Product Monograph
- Low serum albumin;
- Hepatic dysfunction;
- Low bilirubin, low hemoglobin levels, decreased white blood cell count;
- Acidosis, low serum bicarbonate;
- Electrolyte imbalances, hyponatremia and inappropriate ADH (vasopressin) secretion, water intoxication, low fluid intake;
- Presence of brain metastases, prior CNS disease, brain irradiation;
- Cerebral sclerosis, peripheral vasculopathy;
- Presence of tumor in lower abdomen, bulky abdominal disease;
- Poor performance status, advanced age, younger age;
- Obesity, female gender, individual predisposition;
- Interactions with other medicines (e.g. aprepitant, CYP 3A4 inhibitors), alcohol, drug abuse, or pretreatment with cisplatin.
Peri-Operative Considerations
Since ifosfamide may interfere with normal wound healing, Ifosfamide for Injection therapy should not be initiated for at least 10 to 14 days after surgery.
Renal
Ifosfamide is nephrotoxic. Close monitoring of renal function is recommended in patients treated with Ifosfamide for Injection. Ifosfamide should be given cautiously to patients with the following conditions:
- Impaired renal function or reduced nephron reserve
- Abnormal serum creatinine and serum albumin levels
Ifosfamide is contraindicated in patients with severe renal impairment (see CONTRAINDICATIONS) because decreased renal excretion may result in increased plasma levels of ifosfamide and its metabolites. This may result in increased toxicity (e.g. neurotoxicity, nephrotoxicity, hematotoxicity).
Extra care is required in unilaterally nephrectomised patients, in patients with renal tumors and those having undergone renal radiation and in patients with impaired renal function who obviously tolerate high-doses of ifosfamide less well. Such patients have reduced nephron reserve and the risk of developing clinical manifestations of nephrotoxicity is increased. Ifosfamide for Injection should not be given until three months after the nephrectomy.
Acute tubular necrosis, acute renal failure, chronic renal failure secondary to ifosfamide therapy and end-stage renal failure have been reported. Fatal outcome from nephrotoxicity has been documented despite careful monitoring prior to and during therapy.
Disorders of renal function (glomerular and tubular) following ifosfamide administration are very common. Glomerular or tubular dysfunction may resolve with time, remain stable, or progress over a period of months or years, even after completion of ifosfamide treatment. Tubular damage may become apparent during therapy, months or even years after cessation of treatment.
Ifosfamide for Injection – Product Monograph
Renal parenchymal and tubular necrosis have been reported in patients treated with ifosfamide.
Manifestations include a decrease in glomerular filtration rate and an increase in serum creatinine, proteinuria, enzymuria, cylindruria, aminoaciduria, phosphaturia and glycosuria as well as renal tubular acidosis. Fanconi Syndrome, renal rickets and growth retardation in children as well as osteomalacia in adults have also been reported.
Distal tubular dysfunction impairs the ability of the kidney to concentrate urine. Development of a syndrome resembling SIADH (syndrome of inappropriate antidiuretic hormone secretion) has been reported with ifosfamide.
The risk of developing clinical manifestations of nephrotoxicity is increased with, for example:
- large cumulative doses of ifosfamide,
- preexisting renal impairment,
- prior or concurrent treatment with potentially nephrotoxic agents,
- younger age in children (particularly in children up to approximately 5 years of age),
- reduced nephron reserve as in patients with renal tumors and those having undergone renal radiation or unilateral nephrectomy,
- hydronephrosis.
Respiratory
Interstitial pneumonitis and pulmonary fibrosis have been reported with ifosfamide treatment. Other forms of pulmonary toxicity have also been reported. Pulmonary toxicity leading to respiratory failure as well as fatal outcome has been reported.
Sensitivity/Resistance
Anaphylactic/anaphylactoid reactions have been reported in association with ifosfamide. Cross-sensitivity between oxazaphosphorine cytotoxic agents has been reported.
Sexual Function/Reproduction
Patients, male or female, during the reproductive period of life, should be advised of the genotoxic and mutagenic potential of ifosfamide. Women should not become pregnant during therapy with ifosfamide. Men should not father a child during therapy with ifosfamide and for up to 6 months after the end of therapy. Adequate methods of contraception are recommended for such patients (see ADVERSE REACTIONS).
Animal data generated with cyclophosphamide, another oxazaphosphorine cytotoxic agent indicate that exposure of oocytes during follicular development may result in a decreased rate of implantations and viable pregnancies, and in an increased risk of malformations. This effect should be considered in case of intended fertilization or pregnancy after discontinuation of ifosfamide therapy. The exact duration of follicular development in humans is not known, but may be longer than 12 months. Sexually active women and men should use effective methods of contraception during these periods of time.
Ifosfamide interferes with oogenesis and spermatogenesis. Amenorrhea, azoospermia, and
Ifosfamide for Injection – Product Monograph
sterility in both sexes have been reported. Development of sterility appears to depend on the dose of ifosfamide, duration of therapy and the state of gonadal function at the time of treatment. Sterility may be irreversible in some patients.
Female Patients
Amenorrhea has been reported in patients treated with ifosfamide. In addition, with cyclophosphamide, another oxazaphosphorine cytotoxic agent, oligomenorrhea has been reported. The risk of permanent chemotherapy-induced amenorrhea is increased in older women. Girls treated with ifosfamide during prepubescence may develop secondary sexual characteristics normally and have regular menses. Girls treated with ifosfamide during prepubescence subsequently have conceived. Girls who have retained ovarian function after completing treatment are at increased risk of developing premature menopause.
Male Patients
Men treated with ifosfamide may develop oligospermia or azoospermia. Sexual function and libido generally are unimpaired in these patients. Boys treated with ifosfamide during prepubescence may develop secondary sexual characteristics normally, but may have oligospermia or azoospermia. Some degree of testicular atrophy may occur. Azoospermia may be reversible in some patients, though the reversibility may not occur for several years after cessation of therapy. Men treated with ifosfamide have subsequently fathered children.
The following adverse reactions have been reported with another oxazaphosphorine cytostatic agent: intrauterine death, fetal malformation, fetal toxicity (including myelosuppression, gastroenteritis), premature labor, testicular atrophy, oligomenorrhea.
Skin
Alopecia is a very common, dose-dependent effect of ifosfamide administration. Chemotherapy- induced alopecia may progress to baldness. The hair can grow back, though it may be different in texture or color.
Special Populations
Pregnant Women: Ifosfamide can be teratogenic or cause fetal resorption in experimental animals. The administration of ifosfamide during organogenesis has been shown to have a fetotoxic effect in mice, rats and rabbits and therefore may cause fetal damage when administered to pregnant women. It should not be used in pregnancy, particularly in early pregnancy, unless in the judgement of the physician the potential benefits outweigh the possible risk.
Fetal growth retardation and neonatal anemia have been reported following exposure to ifosfamide-containing chemotherapy regimens during pregnancy. In addition, exposure to cyclophosphamide, another oxazaphosphorine cytotoxic agent, has been reported to cause miscarriage, malformations (following exposure during the first trimester), and neonatal effects, including leukopenia, pancytopenia, severe bone marrow hypoplasia, gastroenteritis and potential malignancies in offspring.
Ifosfamide for Injection – Product Monograph
If ifosfamide is used during pregnancy, or if the patient becomes pregnant while taking this drug or after treatment, the patient should be apprised of the potential hazard to a fetus (see WARNINGS AND PRECAUTIONS, Sexual Function/Reproduction).
Nursing Women: As is the case with the oxazaphosphorine class of alkylating agents, Ifosfamide for Injection is excreted in breast milk and breast feeding should be terminated prior to institution of Ifosfamide for Injection therapy. Ifosfamide toxicity may occur in a breast-fed child. These toxicities include neutropenia, thrombocytopenia, low hemoglobin, and diarrhea.
Geriatrics (> 65 years of age): In elderly patients, monitoring for toxicities and the need for dose adjustment should reflect the higher frequency of decreased hepatic, renal, cardiac, or other organ function, and concomitant diseases or other drug therapy in this population.
A study of patients 40 to 71 years of age indicated that elimination half-life appears to increase with advancing age. This apparent increase in half-life appeared to be related to increases in volume of distribution of ifosfamide with age. No significant changes in total plasma clearance or renal or non-renal clearance with age were reported.
Monitoring and Laboratory Tests
Urinary sediment should be examined at regular intervals for the presence of erythrocytes and other signs of urotoxicity or nephrotoxicity.
Glomerular and tubular kidney function must be evaluated and checked before commencement of therapy, as well as during and after treatment.
Close clinical monitoring of serum and urine chemistries, including phosphorus, potassium, and other laboratory parameters appropriate for identifying nephrotoxicity and urothelial toxicity is recommended. Appropriate replacement therapy should be administered as indicated.
Close hematologic monitoring is recommended. White blood cell count, platelet count, and hemoglobin levels should be obtained prior to each administration and at appropriate intervals after administration.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most common adverse reactions due to ifosfamide include alopecia; nausea and vomiting; hemorrhagic cystitis and hematuria; renal dysfunction and renal structural damage; and myelosuppression manifested by anemia, leukopenia, and thrombocytopenia. In addition central nervous system toxicities are also the most commonly reported adverse reactions. Secondary infections and infestations as well as increased risk for infections are commonly reported due to the myelosuppression and immunosuppression caused by ifosfamide. Hepatotoxicity, phlebitis and neutropenic fever are other commonly reported adverse reactions associated with ifosfamide
Ifosfamide for Injection – Product Monograph
administration. Less common adverse reactions associated with ifosfamide administration include peripheral neuropathy, hypotension, diarrhea, stomatitis, dermatitis, papular rash, fatigue, and cardiotoxicity including cardiac arrest, ventricular fibrillation, ventricular tachycardia, cardiogenic shock, myocardial infarction, cardiac failure, and bundle branch block. The detailed list of adverse reactions and frequencies related to ifosfamide administration are described in the Clinical Trial Adverse Drug Reactions section.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The adverse reactions and frequencies in the two tables below are based on publications in the literature describing clinical experience with fractioned administration of ifosfamide as monotherapy with a total dose of 4 to 12 g/m2 per course.
| Clinical Trial Adverse Reactions | |||
System Organ Class (SOC) | Adverse Reaction | Frequency Category | Percentage (Ratio) |
| Infections and infestations | Infection | Common | 9.9% (112/1128) |
Blood and lymphatic system disorders | Leukopenia 1 (any) | Very common |
|
Leukopenia <1 x 10³/mcL | Very common | 43.5% (267/614) | |
Thrombocytopenia 2 (any) | Very common |
| |
Thrombocytopenia <50 x 103/mcL | Common | 4.8% (35/729) | |
| Anemia 3 | Very common | 37.9% (202/533) | |
| Metabolism and nutrition disorders | Anorexia | Common | 1.1% (15/1317) |
| Nervous system disorders | Central nervous system toxicity 4,5 | Very common | 15.4% (154/1001) |
| Gastrointestinal disorders | Nausea/Vomiting | Very common | 46.8% (443/964) |
Ifosfamide for Injection – Product Monograph
| Hepatobiliary disorders | Hepatotoxicity 6 | Common | 1.8% (22/1190) | |||||||||
| Skin and subcutaneous tissue disorders | Alopecia | Very common | 89.6% (540/603) | |||||||||
| Clinical Trial Adverse Reactions | ||||||||||||
System Organ Class (SOC) | Adverse Reaction | Frequency Category | Percentage (Ratio) | |||||||||
| Renal and urinary disorders | Hemorrhagic cystitis | Very common |
| |||||||||
| Hematuria | ||||||||||||
| Very common | 44.1% (282/640) | ||||||||||
| Very common | 21.3% (33/155) | ||||||||||
| Macrohematuria | ||||||||||||
| Very common | 11.1% (66/594) | ||||||||||
| Common | 5.2% (5/97) | ||||||||||
| Renal dysfunction8 | Very common | - | ||||||||||
| Renal structural damage | Very common | - | ||||||||||
| General disorders and administrative site conditions | Phlebitis 9 | Common | 2.8% (37/1317) | |||||||||
| Neutropenic fever 10 | Common | 1.0% (13/1317) | ||||||||||
| Malaise | Unknown | Unable to calculate | ||||||||||
ADR frequency is based upon the following scale: Very common (≥1/10); Common (≥1/100 - <1/10) | ||||||||||||
1 The following adverse reaction terms have been reported for leukopenia: neutropenia, granulocytopenia, lymphopenia, and pancytopenia. For neutropenic fever, see below.
1a The frequency category of leukopenia is based on the frequency of leukopenia <3 x 10³/mcL (42.5% (150/353) not shown in table) and <1 x 10³/ mcL; a relevant percentage ratio cannot be calculated from the pooled data and thus the conservative frequency category of “Very Common” was included in the table.
2 Thrombocytopenia may also be complicated by bleeding. Bleeding with fatal outcome has been reported.
Ifosfamide for Injection – Product Monograph
2a Frequency of thrombocytopenia is based on the frequency of thrombocytopenia <100 x 10 3 /mcL (12.2% (24/196) not shown in table) and <50 x 10 3/mcL; a relevant percentage ratio cannot be calculated from the pooled data and thus the conservative frequency category of “Very Common” was included in the table.
3 Includes cases reported as anemia and decrease in hemoglobin/hematocrit.
4 Encephalopathy with coma and death has been reported.
5 Central nervous system toxicity was reported to be manifested by the following signs and symptoms: Abnormal behavior, Affect lability, Aggression, Agitation, Anxiety, Aphasia, Asthenia, Ataxia, Cerebellar syndrome, Cerebral function deficiency, Cognitive disorder, Coma, Confusional state, Convulsions, Cranial nerve dysfunction, Depressed state of consciousness, Depression, Disorientation, Dizziness, Electroencephalogram abnormal, Encephalopathy, Flat affect, Hallucinations, Headache, Ideation, Lethargy, Memory impairment, Mood change, Motor dysfunction, Muscle spasms, Myoclonus, Progressive loss of brainstem reflexes, Psychotic reaction, Restlessness, Somnolence, Tremor, Urinary incontinence.
6 Hepatotoxicity was reported as increases in liver enzymes, i.e., serum alanine aminotransferase, serum aspartate aminotransferase, alkaline phosphatase, gamma- glutamyltransferase and lactate dehydrogenase, increased bilirubin, jaundice, hepatorenal syndrome.
7 Frequency of hemorrhagic cystitis is estimated based on the frequency of hematuria. Reported symptoms of hemorrhagic cystitis included dysuria and pollakiuria.
8 Renal dysfunction was reported to be manifested as: Renal failure (including acute renal failure, irreversible renal failure; fatal outcomes have been reported), Serum creatinine increased, BUN increased, Creatinine clearance decreased, Metabolic acidosis, Anuria, Oliguria, Glycosuria, Hyponatremia, Uremia, Creatinine clearance increased. Renal structural damage was reported to be manifested as: Acute tubular necrosis, Renal parenchymal damage, Enzymuria, Cylindruria, Proteinuria.
9 Includes cases reported as phlebitis and irritation of the venous walls.
10 Frequency of neutropenic fever: Includes cases reported as granulocytopenic fever.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
| Clinical Trial Adverse Reactions | |||
System Organ Class (SOC) | Adverse Reaction | Frequency Category | Percentage (Ratio) |
| Nervous system disorders | Peripheral neuropathy | Uncommon |
|
| Cardiac disorders | Cardiotoxicity 1 | Uncommon | 0.5% (7/1317) |
| Vascular disorders | Hypotension 2 | Uncommon | 0.3% (4/1317) |
| Gastrointestinal disorders | Diarrhea | Uncommon | 0.7% (9/1317) |
| Stomatitis | Uncommon | 0.3% (4/1317) | |
| Skin and subcutaneous tissue disorders | Dermatitis | Rare | 0.08% (1/1317) |
| Papular rash | Rare | 0.08% (1/1317) | |
| General disorders and administration site conditions | Fatigue | Uncommon | 0.3% (4/1317) |
Ifosfamide for Injection – Product Monograph
ADR frequency is based upon the following scale: Uncommon (≥1/1,000 - <1/100), Rare (≥1/10,000 - <1/1,000), Very rare (<1/10,000) |
1 Cardiotoxicity was reported as congestive heart failure, tachycardia, and pulmonary edema. Fatal outcome has been reported.
2 Hypotension leading to shock and fatal outcome has been reported.
Post-Market Adverse Drug Reactions
The following adverse reactions have been reported in the post-marketing experience, listed by MedDRA System Organ Class (SOC), then by Preferred Term in order of severity, where feasible.
Infections and infestations: The following manifestations have been associated with myelosuppression and immunosuppression caused by ifosfamide: increased risk for and severity of infections†, pneumonias†, sepsis and septic shock (including fatal outcomes), as well as reactivation of latent infections, including viral hepatitis†, Pneumocystis jiroveci†, Herpes Zoster, Strongyloides, progressive multifocal leukoencephalopathy†, and other viral and fungal infections.
Neoplasms, benign and malignant and unspecified (incl. cysts and polyps): As treatment-related secondary malignancy*, acute leukemia* (acute myeloid leukemia*, acute promyelocytic leukemia*), acute lymphocytic leukemia*, myelodysplastic syndrome, lymphoma (Non-Hodgkin’s lymphoma), sarcomas*, renal cell carcinoma, thyroid cancer
Progressions of underlying malignancies, including fatal outcomes, have been reported.
Blood and lymphatic system disorders: Hematotoxicity*, myelosuppression manifested as bone marrow failure, agranulocytosis; febrile bone marrow aplasia; disseminated intravascular coagulation, hemolytic uremic syndrome, hemolytic anemia, neonatal anemia, methaemoglobinaemia
Immune system disorders: Angioedema*, anaphylactic reaction, immunosuppression, urticaria, hypersensitivity reaction
Endocrine disorders: Syndrome of inappropriate antidiuretic hormone secretion (SIADH)
Metabolism and nutrition disorders: Tumor lysis syndrome, metabolic acidosis, hypokalemia, hypocalcemia, hypophosphatemia, hyperglycemia, polydipsia
Psychiatric disorders: Panic attack, catatonia, mania, paranoia, delusion, delirium, bradyphrenia, mutism, mental status change, echolalia, logorrhea, perseveration, amnesia
Nervous system disorders: Convulsion*, status epilepticus (convulsive and nonconvulsive), reversible posterior leukoencephalopathy syndrome, leukoencephalopathy, extrapyramidal disorder, asterixis, movement disorder, polyneuropathy, dysesthesia, hypoesthesia, paresthesia, neuralgia, gait disturbance, fecal incontinence, dysarthria
Eye disorders: Visual impairment, vision blurred, conjunctivitis, eye irritation
Ifosfamide for Injection – Product Monograph
Ear and labyrinth disorders: Deafness, hypoacusis, vertigo, tinnitus
Cardiac disorders: Cardiotoxicity*, cardiac arrest*, ventricular fibrillation*, ventricular tachycardia*, cardiogenic shock*, myocardial infarction*, cardiac failure*, bundle branch block left, bundle branch block right, pericardial effusion, myocardial hemorrhage, angina pectoris, left ventricular failure, cardiomyopathy*, congestive cardiomyopathy, myocarditis*, arrhythmia*, pericarditis, atrial fibrillation, atrial flutter, bradycardia, supraventricular extrasystoles, premature atrial contractions, ventricular extrasystoles, myocardial depression, palpitations, ejection fraction decreased*, electrocardiogram ST- segment abnormal, electrocardiogram T- wave inversion, electrocardiogram QRS complex abnormal
Vascular disorders: Pulmonary embolism, deep vein thrombosis, capillary leak syndrome, vasculitis, hypertension, flushing, blood pressure decreased
Respiratory, thoracic, and mediastinal disorders: Respiratory failure*, acute respiratory distress syndrome*, pulmonary hypertension*, interstitial lung disease* as manifested by pulmonary fibrosis*, alveolitis allergic, interstitial pneumonitis, pneumonitis*; pulmonary edema*, pleural effusion, bronchospasm, dyspnea, hypoxia, cough
Gastrointestinal disorders: Cecitis, colitis, enterocolitis, pancreatitis, ileus, gastrointestinal hemorrhage, mucosal ulceration, constipation, abdominal pain, salivary hypersecretion
Hepatobiliary disorders: Hepatic failure*, hepatitis fulminant*, veno-occlusive liver disease, portal vein thrombosis, cytolytic hepatitis, cholestasis
Skin and subcutaneous tissue disorders: Toxic epidermal necrolysis, Stevens- Johnson syndrome, palmar-plantar erythrodysesthesia syndrome, radiation recall dermatitis, skin necrosis, facial swelling, petechiae, macular rash, rash, pruritus, erythema, skin hyperpigmentation, hyperhidrosis, nail disorder
Musculoskeletal and connective tissue disorders: Rhabdomyolysis, osteomalacia, rickets, growth retardation, myalgia, arthralgia, pain in extremity, muscle twitching
Renal and urinary disorders: Fanconi syndrome, tubulointerstitial nephritis, nephrogenic diabetes insipidus, phosphaturia, aminoaciduria, polyuria, enuresis, feeling of residual urine
Fatal outcomes from acute and chronic renal failure have been documented.
Reproductive system and breast disorders: Infertility, ovarian failure, premature menopause, amenorrhea, ovarian disorder, ovulation disorder, azoospermia, oligospermia, impairment of spermatogenesis, blood estrogen decreased, blood gonadotrophin increased
Congenital, familial and genetic disorders: Fetal growth retardation
General disorders and administrative site conditions: Multi-organ failure*, general physical deterioration, injection/infusion site reactions including swelling, inflammation, pain, erythema, tenderness, pruritus; chest pain, edema, mucosal inflammation, pain, pyrexia, chills
*Including fatal outcomes
†Severe immunosuppression has led to serious, sometimes fatal, infections.
Ifosfamide for Injection – Product Monograph
DRUG INTERACTIONS
Overview
Activation of prodrug, ifosfamide, to form the active metabolite 4-hydroxyifosfamide is via CYP3A4 and CYP2B6 enzymes in the liver. Concomitant therapy with inducers of CYP3A4 enhances the enzyme expression and may potentially increase the formation of metabolites responsible for cytotoxicity. In contrast, inhibitors of CYP3A4 could interfere with ifosfamide activation and may alter the effectiveness of ifosfamide treatment. Inhibition of CYP3A4 can also lead to increased formation of an ifosfamide metabolite associated with CNS and nephrotoxicity. Metabolism of ifosfamide is an autoinducible process resulting in increased clearance over time.
Alcohol: In some patients, alcohol may increase ifosfamide-induced vomiting and nausea.
Drug-Drug Interactions
Planned coadministration or sequential administration of other substances or treatments that could increase the likelihood or severity of toxic effects (by means of pharmacodynamic or pharmacokinetic interactions) requires careful individual assessment of the expected benefit and the risks. Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention.
Patients being treated with ifosfamide and agents that reduce its activation should be monitored for a potential reduction of therapeutic effectiveness and the need for dose adjustment.
Extra care is required in patients pretreated with nephrotoxic drugs (e.g. cisplatin) who obviously tolerate high-doses of ifosfamide for injection less well. Additional caution is also advisable in patients treated concomitantly with drugs having nephrotoxic potential.
Ifosfamide should be given cautiously to patients who have had prior treatment with other antineoplastic agents.
Ifosfamide for Injection – Product Monograph
| Potential Drug-Drug Interactions | |||
| Name/Class/Category | Ref | Effect | Clinical Comment |
| Aprepitant | L | Inducer and moderate inhibitor of CYP3A4. | Reduced activation and metabolism of ifosfamide may alter the effectiveness of ifosfamide treatment. Inhibition of CYP3A4 can also lead to increased formation of an ifosfamide metabolite associated with CNS and nephrotoxicity. Reports suggest increased ifosfamide neurotoxicity in patients receiving antiemetic prophylaxis with aprepitant. The potential for increased formation of metabolites responsible for cytotoxicity and other toxicities (depending on the enzymes induced) must be considered in case of prior or concomitant treatment with these drugs. Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Carbamazepine, Corticosteroids, Rifampin, Phenobarbital, Phenytoin* | L | Inducers of human hepatic and extrahepatic microsomal enzymes (e.g., cytochrome P450 enzymes) | The potential for increased formation of metabolites responsible for cytotoxicity and other toxicities (depending on the enzymes induced) must be considered in case of prior or concomitant treatment with these drugs. Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Fluconazole, Itraconazole, Ketoconazole, Sorafenib | L | Inhibitors of CYP 3A4 | Reduced activation and metabolism of ifosfamide may alter the effectiveness of ifosfamide treatment. Inhibition can also lead to increased formation of an ifosfamide metabolite associated with CNS and nephrotoxicity. Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Ifosfamide for Injection – Product Monograph
| Potential Drug-Drug Interactions | |||
| Name/Class/Category | Ref | Effect | Clinical Comment |
| ACE Inhibitors | L | Increased hematotoxicity and/or immunosuppression may result from a combined effect of ifosfamide and ACE inhibitors. ACE inhibitors can cause leukopenia and agranulocytosis. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Acyclovir | L | Increased nephrotoxicity may result from a combined effect of ifosfamide and Acyclovir. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Aminoglycosides | L | Increased nephrotoxicity may result from a combined effect of ifosfamide and Aminoglycosides. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Amiodarone | L | Increased pulmonary toxicity may result from a combined effect of ifosfamide and amiodarone. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Amphotericin B | L | Increased nephrotoxicity may result from a combined effect of ifosfamide and Amphotericin B. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Anthracyclines | L | Increased cardiotoxicity may result from a combined effect of ifosfamide and Anthracyclines. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Antiemetics | L | Additive CNS effects may result from a combined effect of ifosfamide and antiemetics. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Antihistamines | L | Additive CNS effects may result from a combined effect of ifosfamide and antihistamines. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Busulfan | L | An increased risk of developing hemorrhagic cystitis may result from a combined effect of ifosfamide and busulfan. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Ifosfamide for Injection – Product Monograph
| Potential Drug-Drug Interactions | |||
| Name/Class/Category | Ref | Effect | Clinical Comment |
| Carboplatin | L | Increased hematotoxicity and/or immunosuppression may result from a combined effect of ifosfamide and Carboplatin. Increased nephrotoxicity may result from a combined effect of ifosfamide and carboplatin. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Cisplatin | L | Increased hematotoxicity and/or immunosuppression may result from a combined effect of ifosfamide and Cisplatin. Increased nephrotoxicity may result from a combined effect of ifosfamide and cisplatin. Cisplatin-induced hearing loss can be exacerbated by concurrent ifosfamide therapy. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Coumarin derivatives | L | Increased INR (international normalized ratio) has been reported in patients receiving ifosfamide and warfarin. | The concurrent use of ifosfamide may enhance the anticoagulant effect of warfarin and thus raise the risk of hemorrhages. Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Docetaxel | Increased gastrointestinal toxicity has been reported when ifosfamide was administered before docetaxel infusion. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. | |
G-CSF, GM-CSF (granulocyte colony- stimulating factor, granulocyte macrophage colony- stimulating factor) | L | Increased pulmonary toxicity may result from a combined effect of ifosfamide and G-CSF, GM-CSF. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Ifosfamide for Injection – Product Monograph
| Potential Drug-Drug Interactions | |||
| Name/Class/Category | Ref | Effect | Clinical Comment |
Irradiation of the bladder | L | An increased risk of developing hemorrhagic cystitis may result from a combined effect of ifosfamide and irradiation of the bladder. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Irradiation of the cardiac region | L | Increased cardiotoxicity may result from a combined effect of ifosfamide and irradiation of the cardiac region. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Narcotics | L | Additive CNS effects may result from a combined effect of ifosfamide and narcotics. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Natalizumab | L | Increased hematotoxicity and/or immunosuppression may result from a combined effect of ifosfamide and Natalizumab. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Neuroleptics | L | Additive CNS effects may result from a combined effect of ifosfamide and neuroleptics. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Sedatives | L | Additive CNS effects may result from a combined effect of ifosfamide and sedatives. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Selective serotonin reuptake inhibitors | L | Additive CNS effects may result from a combined effect of ifosfamide and selective serotonin reuptake inhibitors. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
Tricyclic antidepressants | L | Additive CNS effects may result from a combined effect of ifosfamide and tricyclic antidepressants. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
| Vaccines | L | The immunosuppressive effects of ifosfamide can be expected to reduce the response to vaccination. Use of live vaccines may lead to vaccine-induced infection. | Patients receiving such combinations must be monitored closely for signs of toxicity to permit timely intervention. |
*These are examples of drugs that may induce human hepatic and extrahepatic microsomal enzymes (e.g., cytochrome P450 enzymes) Legend: L = Literature
Ifosfamide for Injection – Product Monograph
Drug-Herb Interactions
Inducers of human hepatic and extrahepatic microsomal enzymes (e.g., cytochrome P450 enzymes): The potential for increased formation of metabolites responsible for cytotoxicity and other toxicities (depending on the enzymes induced) must be considered in case of prior or concomitant treatment with, for example:
- St. John’s Wort
DOSAGE AND ADMINISTRATION
Dosing Considerations
Chemotherapy with Ifosfamide for Injection, as with other drugs used in cancer chemotherapy, is potentially hazardous and fatal complications can occur. It is recommended that it be administered only by physicians aware of the associated risks.
Dosage must be individualized. Doses and duration of treatment and/or treatment intervals depend on the therapeutic indication, the scheme of a combination therapy, the patient’s general state of health and organ function, and the results of laboratory monitoring.
Recommended Dose and Dosage Adjustment
The therapeutic administration of Ifosfamide for Injection should invariably be accompanied by uroprotective treatment with mesna.
The recommended dosage is 2,000 - 2,400 mg/m2 per day over a period of a minimum of 30 minutes, on 5 consecutive days. If a lower daily dosage or the total dosage over a longer period is indicated, Ifosfamide for Injection can be given every other day (days 1, 3, 5, 7 and 9) or on 10 consecutive days in lower doses.
The administration of high single dose infusions is feasible up to 5000-8000 mg/m2/24 h under protection of continuous mesna infusion to reduce the risk of urotoxicity.
A treatment series should be repeated after an interval of not less than 3 - 4 weeks.
The optimal use of ifosfamide in combination with other myelosuppressive agents requires dosage adjustments according to the regimen and schedule to be adopted.
See WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, for information on use in patients with hepatic impairment.
See WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics, for monitoring and dose adjustment in elderly patients.
Administration
Prevention of Cystitis
The concomitant administration of mesna helps to prevent the urotoxic side effects of Ifosfamide for Injection which had previously limited the drug's therapeutic use. Every Ifosfamide for
Ifosfamide for Injection – Product Monograph
Injection regimen should be accompanied by uroprotective treatment with mesna.
Mesna is usually given by intravenous injection concurrently with Ifosfamide for Injection, and 4 and 8 hours afterwards, each dose being 20% of the Ifosfamide for Injection, dose (see Mesna Product Monograph for Dosage and Administration).
During or immediately after administration, adequate amounts of fluid should be ingested or infused to force diuresis in order to reduce the risk of urothelial toxicity (see WARNINGS AND PRECAUTIONS). If urinary excretion appears insufficient, a fast-acting diuretic such as furosemide may be administered.
Reconstitution:
Reconstitute with Sterile Water for Injection as follows:
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
| 1 gram | 20 mL | 20 mL | 50 mg/mL |
| 3 gram | 60 mL | 60 mL | 50 mg/mL |
The pH of freshly reconstituted 5% w/v solutions usually range from 4 to 7.
Directions for Further Dilution:
Preparation for Intravenous Infusion
Shake well until dissolved. The prepared solution may be further diluted to achieve concentrations of 0.6 to 20 mg/mL with any of the solutions for intravenous infusion listed below in PVC bags.
Solutions for Intravenous Infusion:
5% Dextrose Injection, USP
0.9% Sodium Chloride, USP
Lactated Ringer's Injection, USP
NOTE: Product should be inspected visually for particulate matter and discoloration prior to administration.
See STORAGE AND STABILITY, Stability of Solutions.
See SPECIAL HANDLING INSTRUCTIONS.
Ifosfamide for Injection – Product Monograph
OVERDOSAGE
No specific antidote for ifosfamide is known. Ifosfamide as well as ifosfamide metabolites are dialyzable. Management of overdosage would include general supportive measures, including appropriate treatment for any concurrent infection, myelosuppression, or other toxicity, to sustain the patient through any period of toxicity that might occur.
Serious consequences of overdosage include manifestations of dose-dependent toxicities such as CNS toxicity, nephrotoxicity, myelosuppression, and mucositis (see WARNINGS AND PRECAUTIONS). Patients who received an overdose should be closely monitored for the development of toxicities. Cystitis prophylaxis with mesna may be helpful in preventing or limiting urotoxic effects with overdose.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ifosfamide is activated by metabolism in the liver by the mixed-function oxidase system of the smooth endoplasmic reticulum. The activation is induced by hydroxylation at the ring carbon atom 4. Opening of the ring results in the formation of aldo-ifosfamide, the tautomer of 4- hydroxy-ifosfamide. Two stable metabolites, 4-keto-ifosfamide and 4-carboxyifosfamide, appear in the urine. However, they have no cytotoxic activity. N,N’-bis(2-chloroethyl)-phosphoric acid diamide and acrolein are also found. The enzymatic oxidation of the chloroethyl side chains and subsequent dealkylation may produce further metabolites.
DNA is one of the main target sites of Ifosfamide. In vitro, incubation of DNA with activated Ifosfamide produces phosphotriesters as the predominant reaction products. The treatment of intact cell nuclei may also result in the formation of DNA-DNA crosslinks. DNA repair occurs in G-1 and G-2 stage cells. Repair capacity is more marked in less sensitive tumours. An accumulation of cells in the G-1 phase is found in tumours that respond well.
STORAGE AND STABILITY
Store Ifosfamide for Injection vials at room temperature between 15 °C and 25 °C. Protect from temperatures above 30 °C.
Stability of Solutions
Reconstituted solutions should be used within 24 hours if stored at room temperature, or within 72 hours if refrigerated. Use further diluted solutions immediately.
Ifosfamide for Injection – Product Monograph
NOTE: As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discolouration and leakage prior to administration, whenever solution and container permit. Solution showing haziness, particulate matter, precipitate, discolouration or leakage should not be used. Discard unused portion.
SPECIAL HANDLING INSTRUCTIONS
Handling and Disposal
Preparation of Ifosfamide for Injection should be done in a vertical laminar flow hood (Biological Safety Cabinet - Class II).
Personnel preparing ifosfamide should wear PVC gloves, safety glasses, disposable gowns and masks. Reconstitution and administration should be undertaken only by trained personnel. Pregnant staff and breastfeeding mothers should be excluded. If ifosfamide solution contacts the skin or mucosa, immediately wash the skin thoroughly with soap and water or rinse the mucosa with copious amounts of water, and seek medical attention.
All needles, syringes, vials and other materials which have come in contact with Ifosfamide for Injection should be segregated and incinerated at 1,000°C or more. Sealed containers may explode while still sealed. Intact vials should be returned to the Manufacturer for destruction. Proper precautions should be taken in packaging these materials for transport.
Personnel regularly involved in the preparation and handling of ifosfamide should have bi-annual blood examinations.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Ifosfamide for Injection is available as sterile lyophilized powder supplied in 1 g and 3 g vials. Vial stoppers do not contain natural rubber latex.
Composition
Ifosfamide for Injection vials contain ifosfamide sterile powder.
AVAILABILITY OF DOSAGE FORMS
C104210 1 g single-dose vial in 30 mL vial, packaged individually
C104300 3 g single-dose vial in 100 mL vial, packaged individually
Ifosfamide for Injection – Product Monograph
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common Name: Ifosfamide
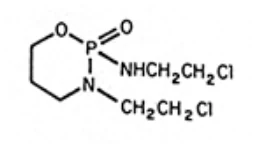
Chemical Name: 3-(2-chloroethyl)-2-[(2-chloroethyl)amino]tetrahydro-2H-1,3,2- oxazaphosphorine-2-oxide
Structural Formula:
Molecular Formula: C7 H15Cl2N2O2P
Molecular Weight: 261.09
Description: Ifosfamide belongs to the family of oxazaphosphorine nitrogen mustards.
It is a white crystalline powder, soluble in water or saline.
pH of 10% solution (w/v) is 4.5 - 7.0. Melting Range: 48.0 °C − 51.0 °C.
DETAILED PHARMACOLOGY
Human Data
The terminal plasma half-lives have been shown to be dose dependent. At lower doses, the terminal plasma half lives ranged from 4 - 7 hours. At higher doses (3.8 - 5.0 gm/m2), a bi- phasic decrease in plasma levels of unchanged drug was observed with a terminal half-life of about 15 hours. Clearance of unchanged drug was 21 mL/min. Maximal plasma concentrations of alkylating ifosfamide metabolites occurred at 3 hours after dosage. Approximately one-half of the dose was recovered in the urine unchanged while 20 - 36% was excreted in the urine as metabolites. At doses of 5 g/m2 and above, it appears that the processes responsible for metabolism of ifosfamide are saturated. Two monodechloroethylated derivatives as well as carboxyifosfamide have been identified in urine as major metabolites.
Ifosfamide for Injection – Product Monograph
A multicompartment pharmacokinetic model has been used to describe the disposition of the drug, and it was calculated that the apparent volume of distribution for the central and peripheral tissue compartments was about 32 and 15 litres, respectively. Volume of distribution for ifosfamide metabolites was observed to approximate plasma volume, which may be due to very high plasma protein binding. Although ifosfamide was found in cerebrospinal fluid, its concentration there was much less than in plasma and negligible amounts of ifosfamide metabolites were found in cerebrospinal fluid.
Differences were evident in the pharmacokinetics of ifosfamide when the drug was administered singly (3.8 - 5 g/m2) or in smaller multiple daily doses (1.6 - 2.4 g/m2/day). In the latter case with equal intravenous doses on three consecutive days, a monoexponential plasma level decay curve with a much shorter half-life than that found after single high dosage was observed. The half-life decreased from 8.3 hours, on Day 1 to 6.3 hours on Day 3 of the multiple dose study. Urinary excretion was mainly in the form of ifosfamide metabolites rather than unchanged drug. These observations suggest that ifosfamide induces its own hepatic microsomal metabolism.
The pharmacokinetic profiles of a three-day course of ifosfamide therapy and a second course of therapy 21 days later were similar.
A study of patients 40 to 71 years of age indicated that elimination half-life appears to increase with advancing age. This apparent increase in half-life appeared to be related to increases in volume of distribution of ifosfamide with age. No significant changes in total plasma clearance or renal or non-renal clearance with age were reported.
Animal Data
Ifosfamide labelled with 14C given intravenously to dogs shows a half-life of less than 30 minutes and in one hour the serum isotope level is less than l0% of the peak level. Total urinary recovery is about 84% of which only a small fraction is unaltered drug.
TOXICOLOGY
Acute Toxicity
Acute Toxicity of Ifosfamide in Various Species
| Species | Route | LD50 (mg/kg) |
| Mouse | intraperitoneal | 520 |
| Mouse | intravenous | 741 |
| Rat | intravenous | 160 |
| Rat | intraperitoneal | 150 - 190 |
| Rabbit | intravenous | 200 |
| Dog | intravenous | 20 - 40 |
Abnormalities noted for the mice in the lethal range were ataxia, labored respiration, hypoactivity and exophthalmos. In rats, the following morphological effects were noted: necrosis in the germinal centers of the cervical and mesenteric lymph nodes and spleen, atrophy of the
Ifosfamide for Injection – Product Monograph
spleen, irritation of the urinary bladder, congestion, hemorrhage, bone marrow depression and focal necrosis in the cortex of the thymus. A study made of the acute intravenous toxicities of ifosfamide showed adverse reactions of hypoactivity and emesis.
Subacute Toxicity
Subacute studies on 10 male and 10 female mice (5 daily doses intraperitoneally, 36 day observation period) gave an LD50 value of 145 mg/kg (delayed deaths). Lesions were frequently seen in the liver and occasionally in the spleen and urinary bladder in the two highest dose groups (238 and 173 mg/kg). Liver abnormalities consisted of necrosis of the hepatic parenchyma, inflammatory hepatitis, focal fatty metamorphosis, and mineralization.
Studies on 10 male and 10 female rats (4 weeks, oral) revealed no mortality, no gross pathology and only slight fatty infiltrations of the liver in the high dose treated group (l0 mg/kg).
The highest non-toxic-intravenous dose of ifosfamide in pairs of male and female young beagle dogs (5 consecutive daily doses) was 4.12 mg/kg. Clinical signs of toxicity were tachycardia, anorexia and dehydration. A value of 2.06 mg/kg for the highest non-toxic intravenous dose was obtained in beagle dogs who received a series of 5 consecutive daily doses of ifosfamide followed by 9 days of rest and another set of 5 consecutive daily doses of ifosfamide. Clinical signs of toxicity were tachycardia, anorexia and dehydration.
The highest non-toxic dose of ifosfamide given on 14 consecutive days to rhesus monkeys by intravenous injection was about 1.03 mg/kg. Histopathologic signs of kidney damage were seen in only the monkey that died. Marked leukopenia occurred in the high dose female only.
Chronic Toxicity
Chronic studies on 15 male and 15 female rats dosed intraperitoneally (25, 50 or 100 mg/kg once every 3 weeks for 6 months) showed myelosuppressive effects on testes, cystitis, enteritis or lung congestion. It is believed that the latter two pathologies may be related to the immunosuppressive properties of ifosfamide and infection. Clinical signs of toxicity were rough haircoats, ataxia and substantial weight losses prior to death. Treatment related microscopic changes included cystitis, lymphoid atrophy in the lymph nodes and spleen, thymus involution, decreased bone marrow cellularity and decreased spermatogenesis. The major contributory causes of death during the study were cystitis; enteritis and pneumonia.
Relative to the chronic toxicity studies in rats, studies in 3 male and 3 female beagle dogs (oral
6 days/week x 26 weeks) demonstrated that the high dose group tolerated the drug well. One female dog of the high dose group died of "distemper-pneumonia". Testicular atrophy was noted in male dogs and most of the treated dogs showed signs of kidney pathology, mainly fatty infiltration of the medullary cortex.
Groups of 3 male and 3 female beagle dogs treated with ifosfamide intravenously (5, 10, 20 mg/kg once every 3 weeks for 6 months) showed hematologic changes, lung pathology, cystitis and renal pathology. The most consistent alterations observed clinically, and at necropsy involved the lungs. Several treated dogs developed rales and necropsy revealed dark or consolidated areas on the lungs of dogs in all groups. The lung lobes of the one high dose male
Ifosfamide for Injection – Product Monograph
that died were dark, firm and congested.
Reproductive Toxicology
Fetal toxicity in rats was noted with ifosfamide (10 and 20 mg/kg doses, intraperitoneally on day 11 of gestation). Ifosfamide (45 mg/kg subcutaneously as a single dose) decreased the rate of body growth and development in one day old drug-treated mice.
Embryotoxicity and teratogenic effects in rabbits were observed with ifosfamide (7.5, 15 or 30 mg/kg intravenously on days 6 - 18 after breeding).
Embryolethal effects and maternal toxicity were evident in pregnant female rats with ifosfamide administration at 9 mg/kg intraperitoneally. No teratogenic effects were observed in fetuses from dams given 1.0 or 3.0 mg/kg of ifosfamide.
Special Studies
Injections of ifosfamide into veins of the rat tail, the rabbit ear and the dog forepaw were well tolerated.
Carcinogenicity
Carcinogenicity studies with ifosfamide conducted on 35 male and 35 female mice (10 to 20 mg/kg per dose intraperitoneally 3 times a week x 52 weeks) showed a significant dose-related increase in the incidence of malignant lymphomas in female mice.
Similar studies done on 35 male and 35 female rats (6 or 12 mg/kg per dose intraperitoneally 3 times a week x 52 weeks) revealed the drug to be carcinogenic. There was a greater incidence of malignant lymphomas and granulocytic leukemias in males. These differences were not statistically significant. On the other hand, in females, there was a greater incidence of leiomyosarcomas and mammary fibroadenomas. These differences were statistically significant.
Ifosfamide for Injection – Product Monograph
REFERENCES
- 1. Brock N, Stekar J, Pohl J, Niemeyer U and Scheffler G. Acrolein, the causative factor of urotoxic side-effects of cyclophosphamide, ifosfamide, trofosfamide and sufosfamide. Drug Res 1979; 29:659-661.
- 2. Cox PJ. Cyclophosphamide cystitis - Identification of acrolein as the causative agent. Biochem Pharmacol 1979; 28:2045-9.
- 3. Hoefer-Janker H, Scheef W, Gunther U and Heels W. Erfahrungen mit der fraktionierten ifosfamid-stro therapie bei generalisierten malignen tumoren. Med Welt 1975; 26:972-9.
- 4. Brock N, Pohl J and Stekar J. Studies on the urotoxicity of oxazaphosphorine cytostatics and its prevention-I. Experimental studies on the urotoxicity of akylating compounds. Eur J Cancer 1981; 17:595-607.
- 5. Connors TA. Protection against the toxicity of akylating agents by thiols: the mechanism of protection and its relevance to cancer chemotherapy. A review. Eur J Cancer 1966; 2:293-305.
- 6. Brock N, Pohl J and Stekar J. Studies on the urotoxicity of oxazaphosphorine cytostatics and its prevention. Comparative study on the uroprotective efficacy of thiols and other sulfur compounds. Eur J Cancer 1981; 17:1155-1163.
- 7. Brade WP, Herdrich K and Varini M. Ifosfamide - pharmacology, safety and therapeutic potential. Cancer Treatment Reviews 1985; 12:1-47.
- 8. Buxton EJ, Meanwell CA, Hilton C, Mould JJ, et al. Combination Bleomycin, Ifosfamide, and Cisplatin Chemotherapy in Cervical Cancer. Journal of National Cancer Institute 1989; 81:5:359-361.
- 9. Coleman RE, Harper PG, Gallagher C, Osborne, R, et al. A phase II study of ifosfamide in advanced and relapsed carcinoma of the cervix. Cancer Chemother Pharmacol 1986; 18:280-283.
- 10. Buxton EJ, Blackledge G, Mould JJ, Monaghan J, et al. The Role of Ifosfamide in Cervical Cancer. Seminars in Oncology 1989; 16:1:3:60-67.
- 11. Sutton GP, Blessing JA, Photopulos G, Berman L, Homesley HD. Phase II Experience with Ifosfamide/ Mesna in Gynecologic Malignancies: Preliminary Report of Gynecologic Oncology Group Studies. Seminars in Oncology 1989; 16:1:3:68-72.
- 12. Baxter Corporation, Product Monograph: Ifex, Control No: 213560, Date of Revision June 27, 2018.