


Product Monograph - Invega Sustenna
RECENT MAJOR LABEL CHANGES
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | 09/2023 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .................................................................................... 2
TABLE OF CONTENTS .......................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................. 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics ............................................................................................................ 4
1.2 Geriatrics ............................................................................................................ 4
2 CONTRAINDICATIONS .............................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................... 5
4 DOSAGE AND ADMINISTRATION ............................................................................. 5
4.1 Dosing Considerations ....................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .................................................. 6
4.4 Administration ..................................................................................................... 9
4.5 Missed Dose ..................................................................................................... 13
5 OVERDOSAGE ......................................................................................................... 14
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................. 15
7 WARNINGS AND PRECAUTIONS ........................................................................... 16
7.1 Special Populations .......................................................................................... 24
7.1.1 Pregnant Women ........................................................................................ 24
7.1.2 Breast-feeding ............................................................................................ 24
7.1.3 Pediatrics .................................................................................................... 25
7.1.4 Geriatrics .................................................................................................... 25
8 ADVERSE REACTIONS ............................................................................................ 26
8.1 Adverse Reaction Overview ............................................................................. 26
8.2 Clinical Trial Adverse Reactions ....................................................................... 26
8.3 Less Common Clinical Trial Adverse Reactions .............................................. 35
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ....................................................................................................... 37
8.5 Post-Market Adverse Reactions ....................................................................... 37
9 DRUG INTERACTIONS ............................................................................................. 39
9.2 Drug Interactions Overview .............................................................................. 39
9.3 Drug-Behavioural Interactions .......................................................................... 40
9.4 Drug-Drug Interactions ..................................................................................... 40
9.5 Drug-Food Interactions ..................................................................................... 42
9.6 Drug-Herb Interactions ..................................................................................... 42
9.7 Drug-Laboratory Test Interactions .................................................................... 42
10 CLINICAL PHARMACOLOGY .................................................................................. 42
10.1 Mechanism of Action ........................................................................................ 42
10.2 Pharmacodynamics .......................................................................................... 42
10.3 Pharmacokinetics ............................................................................................. 43
11 STORAGE, STABILITY AND DISPOSAL ................................................................. 48
12 SPECIAL HANDLING INSTRUCTIONS .................................................................... 48
PART II: SCIENTIFIC INFORMATION .................................................................................. 49
13 PHARMACEUTICAL INFORMATION ....................................................................... 49
14 CLINICAL TRIALS .................................................................................................... 50
14.1 Clinical Trial by Indication ................................................................................. 50
Schizophrenia ............................................................................................................ 50
Schizoaffective Disorder ............................................................................................ 52
15 MICROBIOLOGY ....................................................................................................... 54
16 NON-CLINICAL TOXICOLOGY ................................................................................ 54
PATIENT MEDICATION INFORMATION ............................................................................. 56
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Adults
INVEGA SUSTENNA® (paliperidone palmitate prolonged-release injectable suspension) is indicated for:
- the treatment of schizophrenia. In controlled clinical trials, Invega Sustenna was found to improve the symptoms of schizophrenia, including positive and negative symptoms.
- maintenance treatment of schizoaffective disorder. The efficacy of Invega Sustenna in maintaining symptomatic control for up to 15 months was demonstrated in a double-blind, placebo controlled clinical trial of adult patients with schizoaffective disorder who were first stabilized on Invega Sustenna during 6 months of open-label treatment.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Invega Sustenna in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use and its use is not recommended. See 7.1.3 Pediatrics.
1.2 Geriatrics
Geriatrics (> 65 years of age): Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. Invega Sustenna is not indicated for the treatment of elderly patients with dementia. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
Invega Sustenna is contraindicated in patients who are hypersensitive to paliperidone, risperidone, or to any other ingredient in the formulation or component of the container (see 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity, and 8.5 Post-Market Adverse Reactions). For a complete listing of ingredients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Increased Mortality in Elderly Patients with Dementia Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of thirteen placebo-controlled trials with various atypical antipsychotics (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature (see 7.1.4 Geriatrics, Use in Geriatric Patients with Dementia). Invega Sustenna is not indicated for the treatment of elderly patients with dementia. |
4 DOSAGE AND ADMINISTRATION
Invega Sustenna is only to be administered by intramuscular injection in the gluteal or deltoid muscle by a Healthcare Professional. Care must be taken to avoid inadvertent injection of Invega Sustenna into a blood vessel (see 4.4 Administration).
4.1 Dosing Considerations
For patients who have never taken oral paliperidone or oral/injectable risperidone, tolerability with oral paliperidone or oral risperidone should be established prior to initiating treatment with Invega Sustenna.
Hypersensitivity
Very rare cases of severe hypersensitivity after injection with Invega Sustenna have been reported during post-marketing experience in patients who have previously tolerated oral paliperidone or oral risperidone. Care should be taken to avoid exposure to those that are suspected to be hypersensitive or have shown hypersensitivity reactions to any of the excipients (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
Concomitant use with risperidone, oral paliperidone, or other antipsychotics
There are no systematically collected safety data to specifically address concomitant use of Invega Sustenna with risperidone, oral paliperidone, or other antipsychotics. Since paliperidone is the major active metabolite of risperidone, caution should be exercised when Invega Sustenna is co-administered with risperidone or oral paliperidone.
Endocrine and metabolic effects
Hyperglycemia and diabetes mellitus have been reported with atypical antipsychotic drugs, including Invega Sustenna.
- Blood glucose should be tested at the beginning of treatment and periodically thereafter in patients with risk factors for diabetes mellitus.
- Patients with a diagnosis of diabetes mellitus should be periodically monitored for worsening of glucose control.
See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism.
Hematologic effects
Complete blood count (CBC) should be tested frequently during first few months of therapy in patients with a history of a clinically significant low white blood cell count or drug-induced leukopenia/neutropenia. Discontinuation of Invega Sustenna should be considered at the first sign of a clinically significant decline in white blood cell count (WBC) in the absence of other causative factors (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
4.2 Recommended Dose and Dosage Adjustment
Adult
Schizophrenia
Recommended initiation regimen of Invega Sustenna is with a dose of 150 mg on treatment day 1 and 100 mg on day 8 (one week later), both administered in the deltoid muscle in order to attain therapeutic concentrations rapidly (see 10 CLINICAL PHARMACOLOGY). Recommendations for switching from other antipsychotics are provided in the subsection Switching Antipsychotic Agents to follow.
The recommended subsequent monthly maintenance dose is 75 mg; this dose can be higher or lower within the recommended range of 25╪ to 150 mg based on individual patient tolerability and/or efficacy. Starting one month after the second initiation regimen dose, monthly maintenance doses can be administered in either the deltoid or gluteal muscle.
ǂ Not currently available in Canada
Schizoaffective Disorder
Recommended initiation regimen of Invega Sustenna is with a dose of 150 mg on treatment day 1 and 100 mg on day 8 (one week later), both administered in the deltoid muscle in order to attain therapeutic concentrations rapidly (see 10 CLINICAL PHARMACOLOGY). Recommendations for switching from other antipsychotics are provided in the subsection Switching Antipsychotic Agents to follow.
The recommended monthly maintenance dose is within the range of 50 to 150 mg adjusted based on tolerability and/or efficacy. Following the second initiation dose, monthly maintenance doses can be administered in either the deltoid or gluteal muscle.
Adjustment of the maintenance dose may be made monthly. When making dose adjustments, the prolonged-release characteristics of Invega Sustenna should be considered (see 10 CLINICAL PHARMACOLOGY), as the full effect of the dose adjustment may not be evident for several months.
Dosage Adjustments for Special Populations
Patients with Renal Impairment
Invega Sustenna has not been systematically studied in patients with renal impairment (see 10.3 Pharmacokinetics, Special Populations and Conditions). For patients with mild renal impairment (creatinine clearance ≥ 50 to < 80 mL/min), recommended initiation of Invega Sustenna is with a dose of 100 mg on treatment day 1 and 75 mg one week later, both administered in the deltoid muscle. Thereafter, follow with monthly injections of 50 mg in either the deltoid or gluteal muscle, adjusted within the range of 25╪ to 100 mg based on individual patient tolerability and/or efficacy.
ǂ Not currently available in Canada
Invega Sustenna is not recommended in patients with moderate or severe renal impairment (creatinine clearance < 50 mL/min). (see 10.3 Pharmacokinetics, Special Population and Conditions).
Patients with Hepatic Impairment
Invega Sustenna has not been studied in patients with hepatic impairment. Based on a study with oral paliperidone, no dose adjustment is required in patients with mild or moderate hepatic impairment. Paliperidone has not been studied in patients with severe hepatic impairment (see 10.3 Pharmacokinetics, Special Populations and Conditions).
Concomitant use with strong CYP3A4/P-glycoprotein (P-gp) inducers
On initiation of a strong CYP3A4/P-gp inducer (e.g,, carbamazepine), the dose of Invega Sustenna should be re-evaluated and increased if necessary. Conversely, on discontinuation of a strong CYP3A4/P-gp inducer, the dose of Invega Sustenna should be re-evaluated and decreased if necessary. (See 9.4 Drug-Drug Interactions)
Pediatrics
Safety and effectiveness of Invega Sustenna in patients < 18 years of age have not been studied.
Elderly
In general, recommended dosing for elderly patients with normal renal function (≥ 80 mL/min) is the same as for younger adults with normal renal function. As elderly patients may have diminished renal function, dose adjustments may be required according to their renal function status (see Patients with Renal Impairment above).
Other Special Populations
No dose adjustment for Invega Sustenna is recommended based on gender, race, or smoking status.
Switching Antipsychotic Agents
There are no systematically collected efficacy or safety data to specifically address switching patients with schizophrenia or schizoaffective disorder from other antipsychotics to Invega Sustenna or concerning concomitant administration with other antipsychotics.
Discontinuation of the previous antipsychotic should be made in accordance with the appropriate prescribing information.
Switching from Oral Antipsychotics
At the time of initiation of treatment with Invega Sustenna, previous oral antipsychotics can be gradually discontinued.
Invega Sustenna should be started according to the one-week initiation dosing regimen (i.e., the initial 150 mg and 100 mg deltoid injections) as described in 4.2 Recommended Dose and Dosage Adjustment.
Patients previously stabilized on different doses of Invega Extended-Release Tablets can attain similar paliperidone steady-state exposure during maintenance treatment with Invega Sustenna following administration of the initiation regimen as described in 4.2 Recommended Dose and Dosage Adjustment and subsequent monthly doses as shown below:
Table 1: Doses of Invega and Invega Sustenna Needed to Attain Similar Steady-State Paliperidone Exposure During Maintenance Treatment
| Formulation | Invega Extended-Release Tablets | Invega Sustenna Prolonged-Release Injectable Suspension |
|---|---|---|
| Dosing Frequency | Once Daily | Once every 4 weeks |
| Dose (mg) | 12 6 3 | 150 75 25-50 |
Switching from Long-Acting Injectable Antipsychotics
When switching patients currently at steady-state on a long-acting injectable antipsychotic (including Risperdal Consta), initiate Invega Sustenna therapy in place of the next scheduled injection. Invega Sustenna should then be continued at monthly intervals.
The one-week initiation dosing regimen described in 4.2 Recommended Dose and Dosage Adjustment, Adult is not required.
Patients previously stabilized on different doses of Risperdal Consta risperidone powder for Injectable Prolonged-Release Suspension can attain similar active drug steady-state exposure during maintenance treatment with Invega Sustenna monthly doses according to the following:
Table 2: Doses of Risperdal Consta and Invega Sustenna Needed to Attain Similar Active Drug Exposure at Steady-state
| Previous Risperdal Consta Dose | Invega Sustenna Dose |
|---|---|
| 25 mg every 2 weeks | 50 mg monthly |
| 37.5 mg every 2 weeks | 75 mg monthly |
| 50 mg every 2 weeks | 100 mg monthly |
Discontinuation of Invega Sustenna
If Invega Sustenna is discontinued, its prolonged-release characteristics must be considered. As recommended with other antipsychotic medications, the need for continuing existing extrapyramidal symptoms (EPS) medication should be re-evaluated periodically.
4.4 Administration
Parenteral drug products should be inspected visually for foreign matter and discolouration prior to administration.
Invega Sustenna is intended for intramuscular use only. Inject slowly, deep into the muscle. Care should be taken to avoid inadvertent injection into a blood vessel. Each injection should be administered by a health care professional. Administration should be in a single injection. Do not administer the dose in divided injections. Do not administer intravascularly or subcutaneously.
The recommended needle size for administration of Invega Sustenna into the deltoid muscle is determined by the patient’s weight. For those ≥ 90 kg (≥ 200 lb), the 1½-inch, 22 gauge needle is recommended. For those < 90 kg (< 200 lb), the 1-inch, 23 gauge needle is recommended. Deltoid injections should be alternated between the two deltoid muscles.
The recommended needle size for administration of Invega Sustenna into the gluteal muscle is the 1½-inch, 22 gauge needle. Administration should be made into the upper-outer quadrant of the gluteal area. Gluteal injections should be alternated between the two gluteal muscles.
Ensure that there are no signs of leakage or damage prior to administration, including when attaching the needle to the syringe and de-aerating (see Instructions for Use below).
Instructions for Use
The kit contains a prefilled syringe and 2 safety needles (a 1½-inch 22 gauge needle and a 1-inch 23 gauge needle) for intramuscular injection.
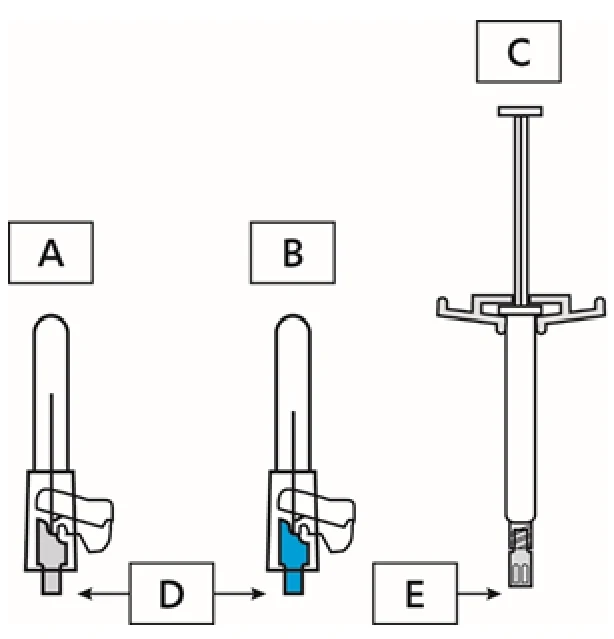
A-22Gx1½″ Gray hub; B-23Gx1″ Blue hub; C-Prefilled Syringe; D-Hub; E-Tip cap
Invega Sustenna is for single use only.
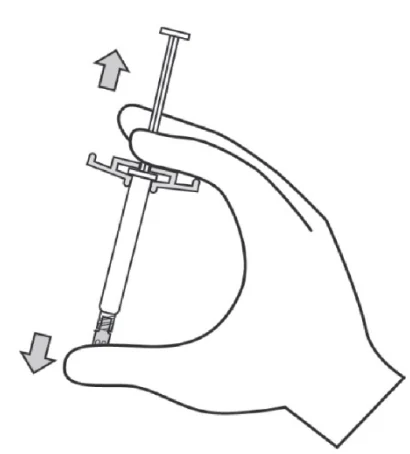
- 1. Shake the syringe vigorously for a minimum of 10 seconds to ensure a homogeneous suspension.
- 2.
Select the appropriate needle.
For DELTOID injection, if the patient weighs < 200 lb (< 90 kg), use the 1-inch 23 gauge needle (needle with blue coloured hub); if the patient weighs ≥ 200 lb (≥ 90 kg), use the 1½-inch 22 gauge needle (needle with gray coloured hub).
For GLUTEAL injection, use the 1½-inch 22 gauge needle (needle with gray coloured hub).
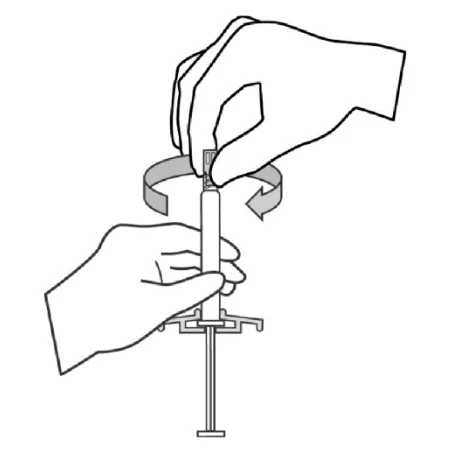
- 3. Hold the syringe with the tip cap pointing up, remove the rubber tip cap with a gentle twisting motion.
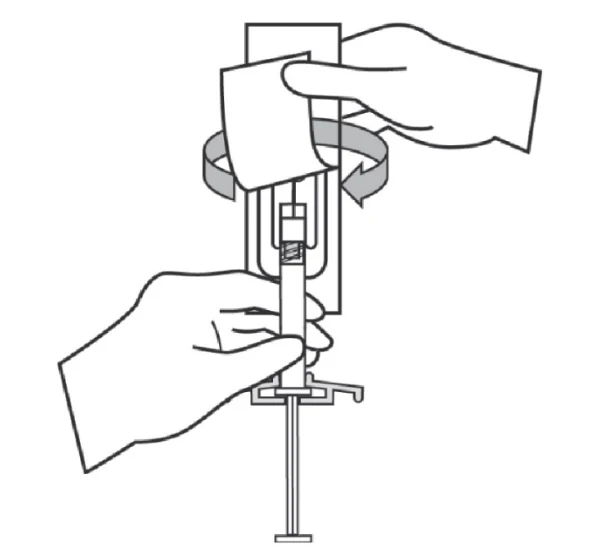
- 4. Peel the safety needle pouch half way open. Grasp the needle sheath using the plastic peel pouch. Hold the syringe pointing up. Attach the safety needle to the syringe using a gentle twisting motion to avoid needle hub cracks or damage. Check for signs of leakage or damage.
- 5. Pull the needle sheath away from the needle with a straight pull. Do not twist the sheath as the needle may be loosened from the syringe.
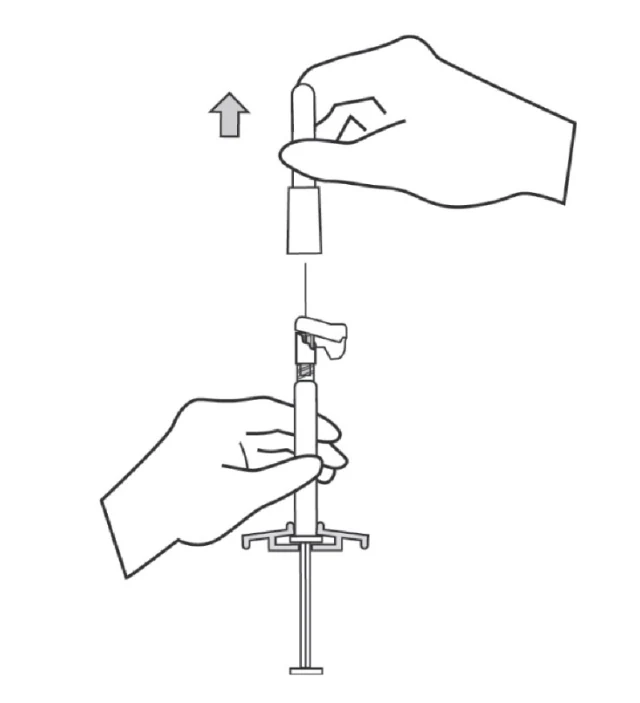
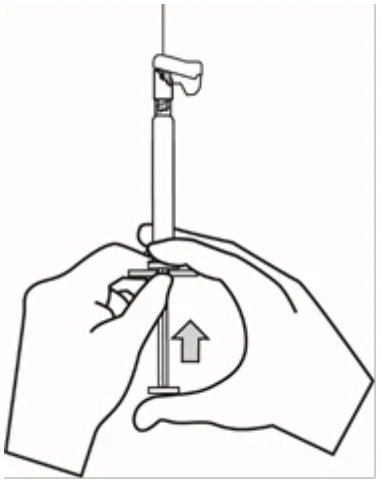
- 6. Bring the syringe with the attached needle in upright position to de-aerate. De-aerate the syringe by moving the plunger rod carefully forward. Check for signs of leakage or damage.
- 7. Inject the entire contents intramuscularly slowly, deep into the selected deltoid or gluteal muscle of the patient. Do not administer intravascularly or subcutaneously.
- 8.
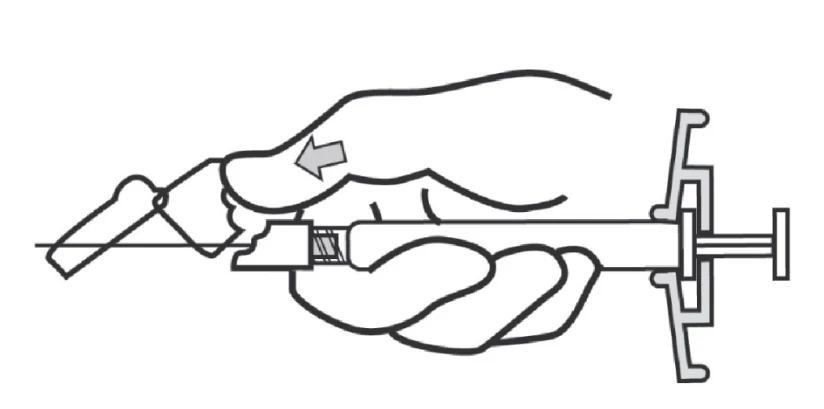
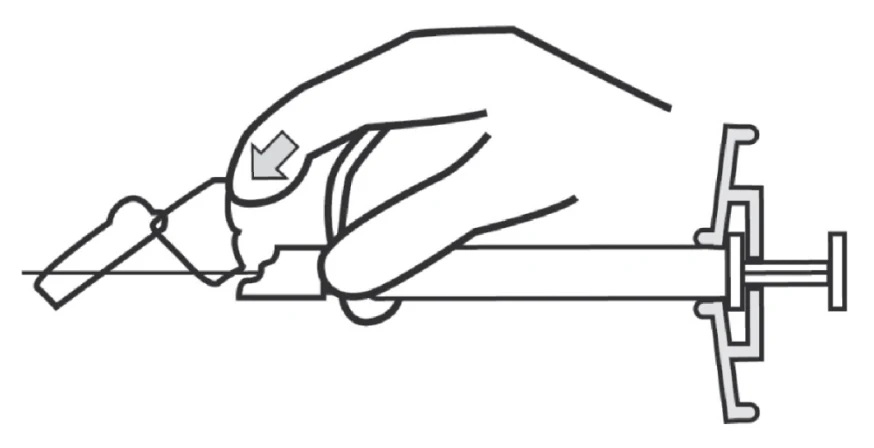
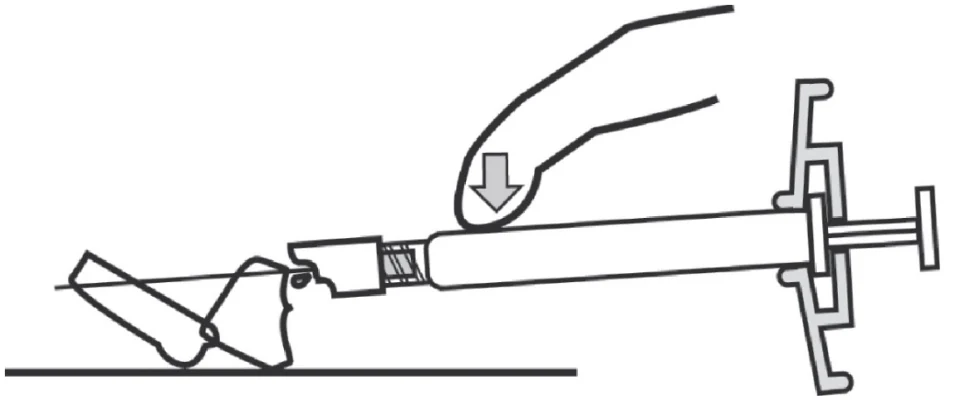
After the injection is complete, use either thumb or finger of one hand (8a, 8b) or a flat surface (8c) to activate the needle protection system. The needle protection system is fully activated when a “click” is heard. Discard the syringe with needle appropriately.
8a
8b
8c
4.5 Missed Dose
Guidance for Avoiding Missed Doses
It is recommended that the second dose of the initiation regimen of Invega Sustenna be given one week after the first dose. To avoid a missed dose, patients may be given the second dose up to 4 days before or after the one-week time point. After the initiation regimen, monthly doses are recommended. To avoid a missed monthly dose, patients may be given the injection up to 7 days before or after the monthly time point.
Guidance for Missed Initiation Regimen Doses
If the target date for the second Invega Sustenna injection (one week ± 4 days) is missed, the recommended re-initiation depends on the length of time which has elapsed since the patient's first injection.
Missed second initiation regimen dose (< 4 weeks from first injection) If less than 4 weeks have elapsed since the first injection, then the patient should be administered the second injection of 100 mg in the deltoid muscle as soon as possible. A third
Invega Sustenna injection of 75 mg in either the deltoid or gluteal muscles should be administered 5 weeks after the first injection (regardless of the timing of the second injection). The normal monthly cycle of injections in either the deltoid or gluteal muscle of 25 mg to 150 mg based on individual patient tolerability and/or efficacy should be followed thereafter.
Missed second initiation regimen dose (4-7 weeks from first injection) If 4 to 7 weeks have elapsed since the first injection of Invega Sustenna, resume dosing with two injections of 100 mg in the following manner:
- 1. a deltoid injection as soon as possible,
- 2. another deltoid injection one week later,
- 3. resumption of the normal monthly cycle of injections in either the deltoid or gluteal muscle of 25 mg to 150 mg based on individual patient tolerability and/or efficacy.
Missed second initiation regimen dose (> 7 weeks from first injection)
If more than 7 weeks have elapsed since the first injection of Invega Sustenna, initiate dosing as described for the initial recommended initiation of Invega Sustenna above.
Guidance for Missed Maintenance Doses
Missed Maintenance Dose (1 Month to 6 Weeks)
After administration of the initiation regimen, the recommended injection cycle of Invega Sustenna is monthly. If less than 6 weeks have elapsed since the last injection, then the previous maintenance dose should be administered as soon as possible, followed by injections at monthly intervals.
Missed Maintenance Dose (> 6 Weeks to 6 Months)
If more than 6 weeks have elapsed since the last injection of Invega Sustenna, the recommendation is as follows:
For patients with previous maintenance doses of 25 to 100 mg:
- 1. a deltoid injection as soon as possible at the same maintenance dose the patient was previously on,
- 2. another deltoid injection (same dose) one week later (day 8),
- 3. resumption of the normal monthly cycle of injections in either the deltoid or gluteal muscle of 25 mg to 150 mg, based on individual patient tolerability and/or efficacy.
For patients with previous maintenance dose of 150 mg:
- 1. a deltoid injection as soon as possible at the 100 mg dose,
- 2. another deltoid injection one week later (day 8) at the 100 mg dose,
- 3. resumption of the normal monthly cycle of injections in either the deltoid or gluteal muscle of 25 mg to 150 mg, based on individual patient tolerability and/or efficacy.
Missed Maintenance Dose (> 6 Months)
Subsequent to administration of the initiation regimen, if more than 6 months have elapsed since the last injection of Invega Sustenna, initiate dosing as described for the initial recommended initiation of Invega Sustenna above.
5 OVERDOSAGE
Because Invega Sustenna is to be administered by health care professionals, the potential for overdosage by patients is low.
Symptoms
In general, expected signs and symptoms are those resulting from an exaggeration of paliperidone’s known pharmacological effects, i.e., drowsiness and sedation, tachycardia and hypotension, QT prolongation, and extrapyramidal symptoms. Torsades de pointes and ventricular fibrillation have been reported in the setting of overdose with oral paliperidone. In the case of acute overdosage, the possibility of multiple drug involvement should be considered.
Treatment
Consideration should be given to the prolonged-release nature of Invega Sustenna and the long apparent half-life of paliperidone when assessing treatment needs and recovery. There is no specific antidote to paliperidone. General supportive measures should be employed. Establish and maintain a clear airway and ensure adequate oxygenation and ventilation. Cardiovascular monitoring should commence immediately and should include continuous electrocardiographic monitoring for possible arrhythmias. Hypotension and circulatory collapse should be treated with appropriate measures such as intravenous fluids and/or sympathomimetic agents. In case of severe extrapyramidal symptoms, anticholinergic agents should be administered. Close supervision and monitoring should continue until the patient recovers.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Dosage Forms and Packaging
Invega Sustenna Prolonged-Release Injectable Suspension contains paliperidone palmitate in pre-filled syringes as a white to off-white sterile aqueous prolonged-release suspension for intramuscular injection. The product is supplied as a kit and contains a prefilled syringe and 2 safety needles, a 1½-inch 22 gauge safety needle, and a 1-inch 23 gauge safety needle. The pre-filled syringes are for single use only.
Composition
The syringes contain 50 mg/0.5 mL, 75 mg/0.75 mL, 100 mg/1 mL or 150 mg/1.5 mL paliperidone (as 78, 117, 156 or 234 mg of paliperidone palmitate respectively).
The inactive ingredients in Invega Sustenna are citric acid monohydrate, disodium hydrogen phosphate anhydrous, polyethylene glycol 4000, polysorbate 20, sodium dihydrogen phosphate
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Intramuscular injection | Prolonged-Release Injectable Suspension Supplied as prefilled syringes containing 50 mg/0.5 mL, 75 mg/0.75 mL, 100 mg/1 mL, and 150 mg/1.5 mL paliperidone as paliperidone palmitate | Citric acid monohydrate, disodium hydrogen phosphate anhydrous, polyethylene glycol 4000, polysorbate 20, sodium dihydrogen phosphate monohydrate, sodium hydroxide, water for injection |
monohydrate, sodium hydroxide, water for injection.
Invega Sustenna should not be mixed with any other product or diluent and is intended for intramuscular administration directly from the syringe in which it is packaged.
7 WARNINGS AND PRECAUTIONS
Please see the 3 SERIOUS WARNINGS AND PRECAUTIONS BOX at the beginning of PART I: HEALTH PROFESSIONAL INFORMATION.
General
Administration
Care must be taken to avoid inadvertent injection of Invega Sustenna into a blood vessel.
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing Invega Sustenna to patients who will be experiencing conditions which may contribute to an elevation in core body temperature, e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration.
Concomitant Use of Invega Sustenna with Risperidone or Oral Paliperidone
There are no systematically collected safety data to specifically address concomitant use of Invega Sustenna with risperidone, oral paliperidone, or other antipsychotics. Since paliperidone is the major active metabolite of risperidone, caution should be exercised when Invega Sustenna is co-administered with risperidone or oral paliperidone.
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use. Aspiration pneumonia is a common cause of morbidity and mortality in patients with advanced Alzheimer’s dementia. Invega Sustenna and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia.
Falls
Somnolence, postural hypotension, motor and sensory instability have been reported with the use of antipsychotics, including Invega Sustenna, which may lead to falls and, consequently, fractures or other fall-related injuries. For patients, particularly the elderly, with diseases, conditions, or medications that could exacerbate these effects, assess the risk of falls when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Carcinogenesis and Mutagenesis
For animal data, see 16 NON-CLINICAL TOXICOLOGY.
Cardiovascular
Orthostatic Hypotension
Paliperidone can induce orthostatic hypotension and syncope in some patients because of its alpha-blocking activity. Syncope was reported in < 1% (4/1293) of subjects treated with Invega Sustenna in the recommended dose range of 25 mg–150 mg in the four fixed-dose, double-blind, placebo-controlled trials compared with 0% (0/510) of subjects treated with placebo. In the long-term study, syncope was not reported as an adverse event in the open-label transition/maintenance phases or the subsequent double-blind phase. However, presyncope was reported as an adverse event in one subject (< 1% [1/849]) in the open-label transition/maintenance phase and syncope was reported as an adverse event in one subject (< 1%) during the open-label extension phase of the study.
In the four short-term fixed-dose, double-blind, placebo-controlled studies in subjects with schizophrenia, orthostatic hypotension was reported as an adverse event by < 1% (2/1293) of Invega Sustenna-treated subjects. Further, 2% (29/1293) of Invega Sustenna-treated subjects in the recommended dose range of 25 mg–150 mg and 2% (11/510) of placebo-treated subjects met predefined criteria for orthostatic hypotension based on vital signs measurements.
In the long-term study in subjects with schizophrenia, there were no reported adverse events of orthostatic hypotension. No more than 1% of Invega Sustenna-treated subjects met the predefined criteria for orthostatic hypotension based on vital signs measurements (1% [6/849]) during the open-label transition/maintenance phases, < 1% [1/205] during the double-blind phase, and 1% [4/388] during the open-label extension phase) compared with 1% (2/203) of placebo-treated subjects in the double-blind phase.
Incidences of orthostatic hypotension and syncope in the long-term study in subjects with schizoaffective disorder were similar to those in the studies in subjects with schizophrenia.
Invega Sustenna should be used with caution in patients with known cardiovascular disease (e.g., heart failure, history of myocardial infarction or ischemia, conduction abnormalities), cerebrovascular disease, or conditions that predispose the patient to hypotension (e.g., dehydration, hypovolemia). Special care should be taken to avoid hypotension in patients with a history of cerebrovascular insufficiency or ischemic heart disease, and in patients taking medications to lower blood pressure.
QT Prolongation
Paliperidone causes a modest increase in the corrected QT (QTc) interval. The use of paliperidone should be avoided in combination with other drugs that are known to prolong QTc including Class 1A (e.g., quinidine, procainamide) or Class III (e.g., amiodarone, sotalol) antiarrhythmic medications, antipsychotic medications (e.g., chlorpromazine, thioridazine), antibiotics (e.g., gatifloxacin, moxifloxacin), or any other class of medications known to prolong the QTc interval. Paliperidone should also be avoided in patients with congenital long QT syndrome and in patients with a history of cardiac arrhythmias.
Certain circumstances may increase the risk of the occurrence of torsades de pointes and/or sudden death in association with the use of drugs that prolong the QTc interval, including (1) bradycardia; (2) hypokalemia or hypomagnesemia; (3) concomitant use of other drugs that prolong the QTc interval; and (4) presence of congenital prolongation of the QT interval.
QT Prolongation Study R076477-SCH-1009
The effects of oral paliperidone on the QT interval were evaluated in a double-blind, active-controlled (moxifloxacin 400 mg single dose), multicentre QT study in adults with schizophrenia and schizoaffective disorder. Serial ECG assessments were scheduled at multiple days and multiple time points during the day. Least square mean changes from baseline in QTcLD were calculated at each scheduled ECG assessment time point and day.
In study R076477-SCH-1009 (n=141), the 8 mg dose of immediate-release oral paliperidone (n=44) showed a maximal (least square) mean change from baseline in QTcLD of 10.9 msec (90% CI: 8.24; 13.62) and was noted on day 8 at 1.5 hours post-dose. The mean steady-state peak plasma concentration for this 8 mg dose of paliperidone immediate release (Cmax ss = 113 ng/mL) was more than 2-fold the exposure predicted for the maximum recommended 150 mg dose of Invega Sustenna administered in the deltoid muscle (predicted median Cmax ss = 50 ng/mL).
In this same study, a 4 mg dose of the immediate-release oral formulation of paliperidone (Cmax ss = 35 ng/mL) showed a maximal (least square) mean change from baseline in QTcLD of 9.3 msec (90% CI: 6.56; 11.98) and was noted on day 2 at 1.5 hours post-dose. None of the subjects had a change exceeding 60 msec or a QTcLD exceeding 500 msec at any time during this study. Also, in this study, a 400 mg dose of moxifloxacin (n=58) showed a maximal least square mean change from baseline in QTcLD of 6.1 msec (90% CI: 3.64; 8.53) and was noted on day 8 at 3 hours post-dose. Placebo (n=58) showed a maximal least square mean change from baseline in QTcLD of 3.5 msec (90% CI: 1.05; 5.95) and was noted on day 2 at 30 minutes post-dose.
In the four fixed-dose, double-blind, placebo-controlled studies of Invega Sustenna in which 1293 subjects with schizophrenia and in the long-term study in which 667 subjects with schizoaffective disorder received active drug, no subject experienced a change in QTcLD exceeding 60 msec and no subject had a QTcLD value of > 500 msec at any time point. In the long-term study in subjects with schizophrenia, in which 849 subjects received Invega Sustenna no subject had a QTcLD change > 60 msec, and one subject had a QTcLD value of 507 msec (Bazett’s QT corrected interval [QTcB] value of 483 msec); this latter subject also had a heart rate of 45 beats per minute.
Driving and Operating Machinery
Somnolence, sedation and dizziness were reported as adverse reactions in subjects treated with Invega Sustenna (see 8 ADVERSE REACTIONS). Antipsychotics, including Invega Sustenna, have the potential to impair judgment, thinking, or motor skills and may have visual effects (e.g., blurred vision). Therefore, patients should be cautioned about performing activities requiring mental alertness and advised not to drive a motor vehicle or operate hazardous machinery until they are reasonably certain that paliperidone therapy does not adversely affect them.
Endocrine and Metabolism
Dyslipidemia
Undesirable alterations in lipids have been observed in patients treated with atypical antipsychotics.
Hyperglycemia and Diabetes Mellitus
Hyperglycemia, diabetes mellitus, and exacerbation of pre-existing diabetes, in some cases extreme and associated with ketoacidosis or hyperosmolar coma or death, have been reported in patients treated with all atypical antipsychotics. These cases were, for the most part, seen in post-marketing clinical use and epidemiologic studies, and not in clinical trials.
Diabetic ketoacidosis (DKA) has occurred in patients treated with antipsychotics with no reported history of hyperglycemia. Appropriate clinical monitoring of patients treated with antipsychotics is advisable in accordance with utilized antipsychotic guidelines.
In clinical trials, there have been reports of hyperglycemia or diabetes (< 3%) in subjects treated with Invega Sustenna. Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia or schizoaffective disorder and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with the atypical antipsychotics. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available.
Any patient treated with atypical antipsychotics, including Invega Sustenna should be monitored for symptoms of hyperglycemia and diabetes mellitus including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Hyperprolactinemia
As with other atypical antipsychotics that antagonize dopamine D2 receptors, paliperidone elevates prolactin levels and the elevation persists during chronic administration. Paliperidone has a prolactin-elevating effect similar to that seen with risperidone.
Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of these drugs is considered in a patient with previously detected breast cancer. Although disturbances such as galactorrhea, amenorrhea, gynecomastia, and impotence have been reported with prolactin- elevating compounds, the clinical significance of elevated serum prolactin levels is unknown for most patients. Long-standing hyperprolactinemia when associated with hypogonadism may lead to decreased bone mineral density in both female and male subjects. As is common with dopamine D2 antagonists, prolonged administration of risperidone in rodent carcinogenicity studies resulted in an increase in the incidence of pituitary gland, mammary gland, and endocrine pancreas hyperplasia and/or tumours (see 16 NON-CLINICAL TOXICOLOGY). However, neither clinical studies nor epidemiologic studies conducted to date have shown an association between chronic administration of this class of drugs and tumorigenesis in humans; the available evidence is considered too limited to be conclusive at this time. The carcinogenic potential of paliperidone, an active metabolite of risperidone, was assessed based on studies with risperidone conducted in mice and rats.
In the four fixed-dose, double-blind, placebo-controlled studies with Invega Sustenna (25 mg–150 mg), the proportion of subjects who experienced potentially prolactin-related adverse events was similar for the placebo (1%) and Invega Sustenna (1–2%) groups.
Weight Gain
Weight gain has been observed with atypical antipsychotic use. Regular clinical monitoring of weight is recommended (see 8.2 Clinical Trial Adverse Reactions, Weight Gain).
Gastrointestinal
Antiemetic Effect
An antiemetic effect was observed in preclinical studies with paliperidone. This effect, if it occurs in humans, may mask the signs and symptoms of overdosage with certain drugs or of conditions such as intestinal obstruction, Reye’s syndrome, and brain tumour.
Genitourinary
Priapism
Drugs with alpha-adrenergic blocking effects have been reported to induce priapism. Priapism has been reported with paliperidone during post-marketing surveillance (see 8.5 Post-Market Adverse Reactions). This adverse reaction, as with other psychotropic drugs, did not appear to be dose-dependent and did not correlate with the duration of treatment.
Although no cases of priapism have been reported in clinical trials with Invega Sustenna, priapism has been reported with oral paliperidone during post-marketing surveillance.
Hematologic
Leukopenia, Neutropenia, and Agranulocytosis
Class Effect: In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including paliperidone. Granulocytopenia and agranulocytosis have also been reported.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) or history of drug-induced leukopenia/neutropenia. Patients with a history of a clinically significant low WBC or a drug-induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and discontinuation of Invega Sustenna should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors.
Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Patients with severe neutropenia (absolute neutrophil count < 1 x 10⁹/L) should discontinue Invega Sustenna and have their WBC counts followed until recovery (see 8.5 Post-Market Adverse Reactions).
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs including Invega Sustenna, in case reports and/or observational studies. When prescribing Invega Sustenna all possible risk factors for VTE should be identified and preventative measures undertaken.
Hepatic/Biliary/Pancreatic
Paliperidone is not extensively metabolized in the liver. Although Invega Sustenna was not studied in patients with hepatic impairment, no dose adjustment is required in patients with mild or moderate hepatic impairment. In a study with oral paliperidone in subjects with moderate hepatic impairment (Child-Pugh class B), the plasma concentrations of unbound paliperidone were similar to those of healthy subjects. Paliperidone has not been studied in patients with severe hepatic impairment.
Immune
Hypersensitivity
There have been very rare spontaneous post-marketing reports of severe hypersensitivity (e.g., anaphylaxis, angioedema, anaphylactic shock) in some patients after injection with Invega Sustenna. It is unknown how many of these patients previously tolerated oral risperidone or paliperidone. However, anaphylactic-type reactions have occurred after administration of injectable paliperidone palmitate in patients who have previously tolerated oral risperidone or oral paliperidone. Symptoms of anaphylaxis include skin rash, hives, peripheral edema, swollen eye, tongue and face, hyperhidrosis, dyspnea, and hypotension. Further treatment with Invega Sustenna should be discontinued if such symptoms occur. Patients with hypersensitivity to oral risperidone, paliperidone, or to any other ingredient of the formulation or component of the container, should not be treated with Invega Sustenna (see 2 CONTRAINDICATIONS). Caution should also be exercised in patients who have had serious allergic reactions to other medications. Prior to initiating treatment with Invega Sustenna tolerability with oral risperidone or oral paliperidone should be established (see 4 DOSAGE AND ADMINISTRATION and 8.5 Post-Market Adverse Reactions). For a complete listing of ingredients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Monitoring and Laboratory Tests
The following assessments should be done periodically during treatment with Invega Sustenna.
- Monitor complete blood count (CBC) in patients with a history of a clinically significant low WBC or a drug-induced leukopenia/neutropenia (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
- Monitor for symptoms of hyperglycemia and diabetes mellitus. Monitor blood glucose, fasting lipid profile and weight as clinically indicated, based on risk factors and/or symptoms (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Neurologic
Extrapyramidal Symptoms (EPS) and Psychostimulants
Caution is warranted in patients receiving both psychostimulants (e.g. methylphenidate) and paliperidone concomitantly, as extrapyramidal symptoms could emerge when adjusting one or both medications. Gradual withdrawal of one or both treatments should be considered (see 9.4 Drug-Drug Interactions).
Neuroleptic Malignant Syndrome (NMS)
Neuroleptic malignant syndrome is a potentially fatal symptom complex that has been reported in association with antipsychotic drugs, including paliperidone.
Clinical manifestations of NMS are hyperthermia, muscle rigidity, altered mental status (including catatonic signs) and evidence of autonomic instability (irregular blood pressure, tachycardia, cardiac arrhythmias, and diaphoresis). Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
In arriving at a diagnosis, it is important to identify cases in which the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.) and untreated or inadequately treated extrapyramidal signs and symptoms. Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
The management of NMS should include: (1) immediate discontinuation of antipsychotic drugs including Invega Sustenna, and other drugs not essential to concurrent therapy; (2) intensive symptomatic treatment and medical monitoring; and (3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment regimens for uncomplicated NMS.
If a patient requires antipsychotic drug treatment after recovery from NMS, the potential reintroduction of drug therapy should be carefully considered. The patient should be carefully monitored, since recurrence of NMS has been reported.
Parkinson’s Disease and Dementia with Lewy Bodies
Physicians should weigh the risks versus the benefits when prescribing antipsychotic drugs, including Invega Sustenna, to patients with Parkinson’s disease or dementia with Lewy bodies (DLB) since both groups may be at increased risk of neuroleptic malignant syndrome as well as having an increased sensitivity to antipsychotic medications. Manifestation of this increased sensitivity can include confusion, obtundation, postural instability with frequent falls, in addition to extrapyramidal symptoms.
Seizures Antipsychotic drugs are known to lower the seizure threshold. In the four short-term fixed-dose, double-blind, placebo-controlled studies in subjects with schizophrenia, < 1% (1/1293) of subjects treated with Invega Sustenna in the recommended dose range of 25 mg–150 mg experienced an adverse event of convulsion compared with < 1% (1/510) of placebo-treated subjects who experienced an adverse event of grand mal convulsion.
In the long-term schizophrenia study, < 1% (3/849) Invega Sustenna-treated subjects in the open-label transition/maintenance phase reported adverse events of convulsion (2 subjects) or epilepsy (1 subject). In the double-blind phase, < 1% (1/205) of Invega Sustenna-treated subjects reported an adverse event of epilepsy compared with 0% (0/203) of placebo-treated subjects. No cases of epilepsy or convulsion were reported in the open-label extension phase of this study.
There were no adverse events of epilepsy or convulsion reported in the long-term study in subjects with schizoaffective disorder.
As with other antipsychotic drugs, Invega Sustenna should be used cautiously in patients with a history of seizures or other conditions that potentially lower the seizure threshold.
Tardive Dyskinesia (TD)
A syndrome of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with antipsychotic drugs. Although TD appears to be most prevalent in the elderly, especially elderly females, it is impossible to predict at the onset of treatment which patients are likely to develop TD. It has been suggested that the occurrence of parkinsonian side effects is a predictor for the development of TD.
The risk of developing TD and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses. There is no known treatment for established cases of TD. The syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. However, antipsychotic treatment itself may suppress the signs and symptoms of TD, thereby masking the underlying process. The effect of symptom suppression upon the long-term course of TD is unknown.
In view of these considerations, Invega Sustenna should be prescribed in a manner that is most likely to minimize the risk of TD. As with any antipsychotic, Invega Sustenna should generally be reserved for patients who appear to be obtaining substantial benefit from the drug. In such patients, the smallest dose and the shortest duration of treatment should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of TD develop during treatment with Invega Sustenna, withdrawal of the drug should be considered. However, some patients may require treatment with Invega Sustenna despite the presence of the syndrome.
Ophthalmologic
Intraoperative Floppy Iris Syndrome
Intraoperative floppy iris syndrome (IFIS) has been observed during cataract surgery in patients treated with medicines with alpha1a-adrenergic antagonist effect, such as Invega Sustenna (see 8.5 Post-Market Adverse Reactions).
This variant of small pupil syndrome is characterized by the combination of a flaccid iris that billows in response to intraoperative irrigation currents, progressive intraoperative miosis despite preoperative dilation with standard mydriatic drugs and potential prolapse of the iris toward the phacoemulsification incisions. IFIS may increase the risk of eye complications during and after the operation. Current or past use of medicines with alpha1a-adrenergic antagonist effect should be made known to the ophthalmic surgeon in advance of surgery. The potential benefit of stopping alpha1 blocking therapy prior to cataract surgery has not been established and must be weighed against the risk of stopping the antipsychotic therapy.
Psychiatric
Suicide
The possibility of suicide or attempted suicide is inherent in psychosis, and thus, close supervision and appropriate clinical management of high-risk patients should accompany drug therapy. Invega Sustenna is to be administered by a health care professional (see 4 DOSAGE AND ADMINISTRATION); therefore, suicide due to an overdose is unlikely.
Renal
Invega Sustenna has not been systematically studied in patients with renal impairment.
The disposition of oral paliperidone was studied in subjects with varying degrees of renal function. Elimination of paliperidone decreased with decreasing creatinine clearance. Total clearance of paliperidone was reduced in subjects with impaired renal function by 32% in mild (CrCl = 50 to < 80 mL/min), 64% in moderate (CrCl = 30 to < 50 mL/min), and 71% in severe (CrCl = 10 to < 30 mL/min) renal impairment, corresponding to an average increase in exposure (AUCinf) of 1.5-fold, 2.6-fold, and 4.8-fold, respectively, compared to healthy subjects. The mean terminal elimination half-life of paliperidone was 24, 40, and 51 hours in subjects with mild, moderate, and severe renal impairment, respectively, compared with 23 hours in subjects with normal renal function (CrCl ≥ 80 mL/min). Based on a limited number of observations with Invega Sustenna in subjects with mild renal impairment (creatinine clearance ≥ 50 to < 80 mL/min) and pharmacokinetic simulations, the dose of Invega Sustenna should be reduced in patients with mild renal impairment (see 4 DOSAGE AND ADMINISTRATION).
Invega Sustenna is not recommended in patients with moderate or severe renal impairment (creatinine clearance < 50 mL/min).
Skin
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and drug reaction with eosinophilia and systemic symptoms (DRESS) are potentially life-threatening adverse drug reactions that have been reported with atypical antipsychotic exposure. SCARs commonly present as a combination of the following symptoms: malaise, mucosal ulceration, extensive cutaneous rash or exfoliative dermatitis, fever, lymphadenopathy and possible eosinophilia. Discontinue Invega Sustenna if severe cutaneous adverse reactions occur (see 8.5 Post-Market Adverse Reactions).
7.1 Special Populations
7.1.1 Pregnant Women
Teratogenic Effects
The safety of intramuscularly-injected paliperidone palmitate or orally-dosed paliperidone for use during human pregnancy has not been established.
A retrospective observational cohort study based on a US claims database compared the risk of congenital malformations for live births among women with and without antipsychotic use during the first trimester of pregnancy. Paliperidone, the active metabolite of risperidone, was not specifically evaluated in this study. Compared to no antipsychotic exposure, the relative risk of congenital malformations with risperidone, after adjusting for confounder variables available in the database, was statistically significant (relative risk = 1.26, 95% CI: 1.02-1.56). No biological mechanism has been identified to explain these findings and teratogenic effects have not been observed in non-clinical studies. Based on the findings of this single observational study, a causal relationship between in utero exposure to risperidone and congenital malformations has not been established. Laboratory animals treated with a high dose of paliperidone showed a slight increase in fetal deaths. Pregnancy parameters were not affected in rats given the intramuscular injection of paliperidone palmitate. The high doses were toxic to the mothers. The offspring were not affected at exposures 20- to 22-fold the maximum human exposure, or intramuscular exposures 6-fold the maximum human exposure.
Non-Teratogenic Effects
Neonates exposed to antipsychotic drugs (including paliperidone) during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
Invega Sustenna should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus. The effect of Invega Sustenna on labour and delivery in humans is unknown.
7.1.2 Breast-feeding
In animal studies with paliperidone and in human studies with risperidone, paliperidone was excreted in the milk. Patients should be advised not to breast-feed an infant if they are taking Invega Sustenna.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of Invega Sustenna in children under the age of 18 years has not been established and its use is not recommended.
Weight gain has been observed with atypical antipsychotic use in pediatric and adolescent patient populations. Independent of any drug-specific effects, weight gain can be associated with adverse changes in other metabolic parameters (e.g., glucose and lipid metabolism). Abnormal childhood weight and metabolic status can have adverse effects on cardiovascular outcomes in adulthood. Weight gain and adverse effects on other metabolic parameters associated with atypical antipsychotics can be more frequent or more severe in pediatric and adolescent patients than in the adult patients.
The long-term safety, including cardiometabolic effects and effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Clinical studies of Invega Sustenna did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between elderly and younger patients.
This drug is known to be substantially excreted by the kidney and clearance is decreased in patients with renal impairment who should be given reduced doses. Because elderly subjects may have diminished renal function, dose adjustments may be required according to their renal function status (see 7 WARNINGS AND PRECAUTIONS, Renal above and 4 DOSAGE AND ADMINISTRATION).
Use in Geriatric Patients with Dementia
Overall Mortality
In a meta-analysis of 13 controlled clinical trials, elderly patients with dementia treated with other atypical antipsychotic drugs had an increased risk of mortality compared to placebo.
Invega Sustenna is not indicated for the treatment of elderly patients with dementia.
Concomitant Use with Furosemide
Invega Sustenna contains paliperidone, the active metabolite of risperidone. In risperidone placebo-controlled trials in elderly patients with dementia, a higher incidence of mortality was observed in patients treated with furosemide plus risperidone when compared to patients treated with risperidone alone.
Invega Sustenna is not indicated for the treatment of elderly patients with dementia.
Cerebrovascular Adverse Events (CVAEs) in Elderly Patients With Dementia
In placebo-controlled trials in elderly patients with dementia treated with some atypical antipsychotic drugs, including risperidone and olanzapine, there was a higher incidence of cerebrovascular adverse events (cerebrovascular accidents and transient ischemic attacks) including fatalities compared to placebo.
Invega Sustenna is not indicated for the treatment of elderly patients with dementia.
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use. Aspiration pneumonia is a common cause of morbidity and mortality in patients with advanced Alzheimer’s dementia. Invega Sustenna and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia.
Invega Sustenna is not indicated for the treatment of elderly patients with dementia.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The data described in this section are derived from a clinical trial database consisting of a total of 3817 subjects with schizophrenia who received at least one dose of Invega Sustenna in the recommended dose range of 25 mg to 150 mg and a total of 510 subjects with schizophrenia who received placebo. Among the 3817 Invega Sustenna-treated subjects, 1293 received Invega Sustenna in four fixed-dose, double-blind, placebo-controlled trials (one 9-week and three 13-week studies), 849 received Invega Sustenna in the long-term trial (median exposure 229 days during the initial 33-week open-label phase of this study, of whom 205 continued to receive Invega Sustenna during the double-blind placebo-controlled phase of this study [median exposure 171 days]), and 1675 received Invega Sustenna in five non-placebo controlled trials (three noninferiority active-comparator trials, one long-term open-label pharmacokinetic and safety study, and an injection site [deltoid-gluteal] cross-over trial). One of the 13-week studies included a 150 mg Invega Sustenna initiation dose followed by treatment with either 25 mg, 100 mg, or 150 mg every 4 weeks.
The safety of Invega Sustenna was also evaluated in a long-term study in adult subjects with schizoaffective disorder. A total of 667 subjects received Invega Sustenna during the initial 25-week open-label period of this study (median exposure 147 days); 164 subjects continued to receive Invega Sustenna during the 15-month double-blind placebo-controlled period of this study (median exposure 446 days).
Adverse events during exposure to study treatment were obtained by general inquiry and recorded by clinical investigators using their own terminology. Consequently, to provide a meaningful estimate of the proportion of individuals experiencing adverse events, events were grouped in standardized categories using MedDRA terminology.
A causal association for Invega Sustenna often cannot be reliably established in individual cases.
The majority of all adverse events were mild to moderate in severity.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Schizophrenia - Short-Term, Placebo-Controlled Studies
The most common adverse events (reported by ≥ 5% in any Invega Sustenna dose group in the four fixed-dose, double-blind, placebo-controlled trials in subjects with schizophrenia and at least twice that for placebo) were: injection site reactions, dizziness, extrapyramidal disorder, somnolence and akathisia.
Discontinuations Due to Adverse Events
In the four short-term fixed-dose, double-blind placebo-controlled schizophrenia trials, 5.0% of subjects treated with Invega Sustenna discontinued due to adverse events as compared to 7.8% of subjects treated with placebo. Schizophrenia (1.5%), psychotic disorder (0.5%), suicidal ideation (0.5%), and agitation (0.5%) were the most common adverse events leading to discontinuation in the Invega Sustenna treatment group. In the overall clinical trial program, one Invega Sustenna-treated subject also discontinued due to neuroleptic malignant syndrome.
Commonly Observed Adverse Drug Events in Double-Blind, Placebo-Controlled Trials
Table 3 enumerates the adverse events reported in ≥ 2% of subjects treated with Invega Sustenna in the four short-term fixed-dose, double-blind, placebo-controlled studies in subjects with schizophrenia.
Table 3: Treatment Emergent Adverse Events in ≥ 2% of Invega Sustenna-Treated Subjects with Schizophrenia in Four Fixed-Dose, Double-Blind, Placebo-Controlled Trials
| Invega Sustenna | Total | ||||||||
| Placebo | 25 mg eq. | 50 mg eq. | 100 mg eq. | 150/25 mg eq. | 150/100 mg eq. | 150/150 mg eq. | Pali | ||
| Body System or Organ Class | (N=510) | (N=130) | (N=302) | (N=312) | (N=160) | (N=165) | (N=163) | (N=1232) | |
| Preferred Term | % | % | % | % | % | % | % | % | |
| Total percentage of subjects with adverse events | 70 | 75 | 68 | 69 | 63 | 60 | 63 | 67 | |
| Infections and infestations | |||||||||
| Bronchitis | 1 | 2 | <1 | 1 | 0 | 1 | 1 | 1 | |
| Influenza | <1 | 0 | 0 | <1 | 2 | 1 | 0 | <1 | |
| Nasopharyngitis | 2 | 0 | 2 | 2 | 4 | 2 | 2 | 2 | |
| Upper respiratory tract infection | 2 | 2 | 2 | 2 | 1 | 2 | 4 | 2 | |
| Urinary tract infection | 1 | 0 | 1 | <1 | 1 | 1 | 2 | 1 | |
| Metabolism and nutrition disorders | |||||||||
| Decreased appetite | 1 | 2 | 1 | 1 | 0 | 1 | 1 | 1 | |
| Psychiatric disorders | |||||||||
| Agitation | 7 | 10 | 5 | 9 | 8 | 5 | 4 | 6 | |
| Anxiety | 7 | 8 | 5 | 3 | 5 | 6 | 6 | 5 | |
| Depression | 1 | 1 | 2 | 1 | 1 | 0 | 1 | 1 | |
| Hallucination, auditory | 1 | 2 | 2 | 1 | 1 | 1 | 1 | 1 | |
| Insomnia | 15 | 15 | 15 | 13 | 12 | 10 | 13 | 13 | |
| Invega Sustenna | Total | ||||||||
| Placebo | 25 mg eq. | 50 mg eq. | 100 mg eq. | 150/25 mg eq. | 150/100 mg eq. | 150/150 mg eq. | Pali | ||
| Body System or Organ Class | (N=510) | (N=130) | (N=302) | (N=312) | (N=160) | (N=165) | (N=163) | (N=1232) | |
| Preferred Term | % | % | % | % | % | % | % | % | |
| Nightmare | <1 | 2 | 0 | 0 | 0 | 0 | 0 | <1 | |
| Suicidal ideation | 2 | 0 | 1 | 2 | 2 | 2 | 1 | 1 | |
| Tension | 1 | 2 | 1 | 1 | 0 | 0 | 0 | 1 | |
| Nervous system disorders | |||||||||
| Akathisia | 3 | 2 | 2 | 3 | 1 | 5 | 6 | 3 | |
| Dizziness | 1 | 6 | 2 | 4 | 1 | 4 | 2 | 3 | |
| Dyskinesia | 1 | 1 | 2 | 1 | 0 | 1 | 1 | 1 | |
| Extrapyramidal disorder | 1 | 5 | 2 | 3 | 1 | 0 | 0 | 2 | |
| Headache | 12 | 11 | 11 | 15 | 11 | 7 | 6 | 11 | |
| Hypertonia | <1 | 1 | 2 | 1 | 0 | 0 | 0 | 1 | |
| Somnolence1 | 3 | 5 | 7 | 4 | 1 | 5 | 5 | 5 | |
| Eye disorders | |||||||||
| Eye swelling | 0 | 2 | 0 | 0 | 0 | 0 | 0 | <1 | |
| Cardiac disorders | |||||||||
| Conduction disorder | 1 | 0 | 2 | 1 | 0 | 0 | 0 | 1 | |
| Sinus bradycardia | 1 | 0 | 1 | <1 | 2 | 0 | 0 | <1 | |
| Tachycardia | <1 | 1 | 0 | 1 | 1 | 1 | 2 | 1 | |
| Vascular disorders | |||||||||
| Hypertension | 1 | 2 | 1 | 1 | 1 | 1 | 0 | 1 | |
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Cough | 1 | 2 | 3 | 1 | 0 | 1 | 1 | 1 | |
| Dyspnea | 1 | 2 | <1 | 1 | 1 | 0 | 0 | 1 | |
| Oropharyngeal pain | 1 | 1 | 2 | <1 | 1 | 1 | 0 | 1 | |
| Gastrointestinal disorders | |||||||||
| Abdominal discomfort/abdominal pain upper1 | 2 | 2 | 4 | 4 | 1 | 2 | 4 | 3 | |
| Constipation | 5 | 3 | 5 | 5 | 2 | 4 | 1 | 4 | |
| Diarrhea | 2 | 0 | 3 | 2 | 1 | 2 | 2 | 2 | |
| Dry mouth | 1 | 3 | 1 | 0 | 1 | 1 | 1 | 1 | |
| Gastroesophageal reflux disease | 0 | 2 | <1 | <1 | 0 | 0 | 0 | <1 | |
| Nausea | 3 | 4 | 4 | 3 | 2 | 2 | 2 | 3 | |
| Toothache | 1 | 1 | 1 | 3 | 1 | 2 | 3 | 2 | |
| Vomiting | 4 | 5 | 4 | 2 | 3 | 2 | 2 | 3 | |
| Invega Sustenna | Total | ||||||||
| Placebo | 25 mg eq. | 50 mg eq. | 100 mg eq. | 150/25 mg eq. | 150/100 mg eq. | 150/150 mg eq. | Pali | ||
| Body System or Organ Class | (N=510) | (N=130) | (N=302) | (N=312) | (N=160) | (N=165) | (N=163) | (N=1232) | |
| Preferred Term | % | % | % | % | % | % | % | % | |
| Skin and subcutaneous tissue disorders | |||||||||
| Pruritus | 1 | 1 | 2 | 1 | 1 | 0 | 1 | 1 | |
| Rash | 1 | 2 | 1 | <1 | 2 | 1 | 2 | 1 | |
| Musculoskeletal and connective tissue disorders | |||||||||
| Back pain | 2 | 2 | 1 | 3 | 1 | 1 | 1 | 1 | |
| Musculoskeletal stiffness | 1 | 1 | <1 | <1 | 1 | 1 | 2 | 1 | |
| Myalgia | 1 | 2 | 1 | <1 | 1 | 0 | 2 | 1 | |
| Pain in extremity | 1 | 0 | 2 | 2 | 2 | 3 | 0 | 2 | |
| General disorders and administration site conditions | |||||||||
| Asthenia | 0 | 2 | 1 | <1 | 0 | 1 | 1 | 1 | |
| Fatigue | 1 | 1 | 2 | 2 | 1 | 2 | 1 | 2 | |
| Injection site reactions1 | 2 | 0 | 4 | 6 | 9 | 7 | 10 | 6 | |
| Pain | 1 | 0 | 2 | 1 | 0 | 1 | 1 | 1 | |
| Investigations | |||||||||
| Alanine aminotransferase increased | 2 | 0 | 2 | 1 | 1 | 1 | 1 | 1 | |
| Aspartate aminotransferase increased | 1 | 0 | 2 | 0 | 1 | 1 | 2 | 1 | |
| Blood cholesterol increased | <1 | 2 | 1 | 0 | 0 | 0 | 0 | <1 | |
| Electrocardiogram QT prolonged | 1 | 1 | 1 | 1 | 2 | 2 | 0 | 1 | |
| Low density lipoprotein increased | <1 | 2 | 1 | 0 | 0 | 1 | 0 | <1 | |
| Weight increased | 1 | 4 | 4 | 1 | 1 | 1 | 2 | 2 | |
| Injury, poisoning and procedural complications | |||||||||
| Skin laceration | <1 | 2 | <1 | 0 | 1 | 0 | 0 | <1 | |
Table includes adverse events reported in 2% or more of any of the Invega Sustenna dose groups and which occurred at an equal or greater incidence than in the placebo group; cut-off criteria (incidence ≥ 2% and ≥ placebo)
are based on percentages after rounding. Note: The adverse events in the studies were coded using the MedDRA version 12.0.
- 1.
The following preferred terms were combined: Somnolence includes: Somnolence and Sedation
Injection site reactions includes: Injection site pain, Injection site pruritus, Injection site nodule, Injection site induration, Administration site pain, Administration site reaction, Application site erythema, Application site swelling, Injection site bruising, Injection site discomfort, Injection site erythema, Injection site extravasation, Injection site inflammation, Injection site irritation, Injection site mass, Injection site oedema, Injection site reaction, Injection site swelling, Injection site hematoma, Injection site joint pain, Vessel puncture site pain, and Vessel puncture site reaction
Abdominal discomfort/Abdominal pain upper includes: Abdominal discomfort, Stomach discomfort, and Abdominal pain upper
Schizophrenia – Long-Term Study
In the long-term trial, the nature and frequencies of adverse events during the open-label phases of this study were generally comparable to those observed in the four placebo-controlled fixed-dose studies shown in Table 3. The nature of adverse events reported during the double-blind phase of this study were also generally similar to those observed in the open-label phases.
Schizoaffective Disorder
The safety profile of Invega Sustenna in patients with schizoaffective disorder is generally similar to that observed in patients with schizophrenia. A larger proportion of all subjects in the open-label period of the long-term study in schizoaffective disorder experienced treatment emergent adverse events of Nervous System Disorders (30%) and General Disorders and Administrative Site Conditions (19%) as compared with all subjects in the open-label period of the long-term study in schizophrenia, where these treatment emergent adverse events were observed in 21%, and 9% of all subjects, respectively. Akathisia, dyskinesia, somnolence, tremor and some injection site reactions were all reported more frequently in subjects with schizoaffective disorder compared to subjects with schizophrenia during the open-label periods of these studies.
The percentage of subjects who discontinued due to adverse events in the open-label period of the long-term study in subjects with schizoaffective disorder was 7.5%. During the double-blind, placebo-controlled period of that study, 5.5% and 1.8% of Invega Sustenna- and placebo-treated subjects, respectively, discontinued treatment due to adverse events.
Adverse events that occurred more frequently during the double-blind period in the Invega Sustenna than the placebo group (a 2% difference or more between groups) were weight increased, nasopharyngitis, headache, hyperprolactinemia, and pyrexia.
The following additional adverse events were also reported by subjects with schizoaffective disorder who received Invega Sustenna during the open-label or double-blind period of the long-term study:
Gastrointestinal disorders: dyspepsia, flatulence
Investigations: blood prolactin increased, weight decreased
Metabolism and nutrition disorders: increased appetite
Musculoskeletal and connective tissue disorders: arthralgia
Respiratory, thoracic and mediastinal disorders: nasal congestion, rhinorrhea
Adverse Events Observed Across Schizophrenia and Schizoaffective Disorder Indications
Dose-Related Adverse Events
Based on the pooled data from the four short-term fixed-dose, double-blind, placebo-controlled trials in subjects with schizophrenia, among the adverse events that occurred at ≥ 2% incidence in the subjects treated with Invega Sustenna, only akathisia and injection site reactions display a clear dose-related trend. Hyperprolactinemia also exhibited a dose relationship, but did not occur at ≥ 2% incidence in subjects treated with Invega Sustenna.
Demographics
An examination of population subgroups in the double-blind, placebo-controlled trials did not reveal any evidence of differences in safety on the basis of age, gender, or race alone; however, there were few subjects ≥ 65 years of age.
Extrapyramidal Symptoms (EPS)
Pooled data from the two double-blind, placebo-controlled, 13-week, fixed-dose trials in subjects with schizophrenia provided information regarding treatment-emergent EPS. Several methods were used to measure EPS: (1) the Simpson-Angus global score (mean change from baseline or score at the end of trial) which broadly evaluates Parkinsonism, (2) the Barnes Akathisia Rating Scale global clinical rating score (mean change from baseline or score at the end of trial) which evaluates akathisia, (3) use of anticholinergic medications to treat emergent EPS, (4) the Abnormal Involuntary Movement Scale scores (mean change from baseline or scores at the end of trial) (Table 4), and (5) incidence of spontaneous reports of EPS (Table 5).
Table 4: Treatment-Emergent Extrapyramidal Symptoms (EPS) Assessed by Incidence of Rating Scales and Use of Anticholinergic Medication – Schizophrenia Studies
| Percentage of Subjects | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Invega Sustenna | ||||||||||
| Placebo | 25 mg | 50 mg | 100 mg | |||||||
| Scale | (N=262) | (N=130) | (N=223) | (N=228) | ||||||
| Parkinsonism1 | 9 | 12 | 10 | 6 | ||||||
| Akathisia2 | 5 | 5 | 6 | 5 | ||||||
| Dyskinesia3 | 3 | 4 | 6 | 4 | ||||||
| Use of Anticholinergic Medications4 | 12 | 10 | 12 | 11 | ||||||
- 1. For Parkinsonism, percent of subjects with Simpson-Angus Total score > 0.3 at endpoint (Total score defined as total sum of items score divided by the number of items)
- 2. For Akathisia, percent of subjects with Barnes Akathisia Rating Scale global score ≥ 2 at endpoint
- 3. For Dyskinesia, percent of subjects with a score ≥ 3 on any of the first 7 items or a score ≥2 on two or more of any of the first 7 items of the Abnormal Involuntary Movement Scale at endpoint
- 4. Percent of subjects who received anticholinergic medications to treat emergent EPS
Table 5: Treatment-Emergent Extrapyramidal Symptoms (EPS)-Related Adverse Events by MedDRA EPS Group Term – Schizophrenia Studies
| Percentage of Subjects | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Invega Sustenna | ||||||||||
| Placebo | 25 mg | 50 mg | 100 mg | |||||||
| EPS Group | (N=262) | (N=130) | (N=223) | (N=228) | ||||||
| Overall percentage of subjects with EPS-related adverse events | 10 | 12 | 11 | 11 | ||||||
| Parkinsonism1 | 5 | 6 | 6 | 4 | ||||||
| Hyperkinesia2 | 2 | 2 | 2 | 4 | ||||||
| Tremor | 3 | 2 | 2 | 3 | ||||||
| Dyskinesia3 | 1 | 2 | 3 | 1 | ||||||
| Dystonia4 | 0 | 1 | 1 | 2 | ||||||
- 1. Parkinsonism group includes: Extrapyramidal disorder, hypertonia, musculoskeletal stiffness, parkinsonism, drooling, masked facies, muscle tightness, hypokinesia
- 2. Hyperkinesia group includes: Akathisia, restless legs syndrome, restlessness
- 3. Dyskinesia group includes: Dyskinesia, choreoathetosis, muscle twitching, myoclonus, tardive dyskinesia
- 4. Dystonia group includes: Dystonia, muscle spasms
The results across all phases of the long-term trial in subjects with schizophrenia exhibited comparable findings. In the 9-week, fixed-dose, double-blind, placebo-controlled trial, the proportions of Parkinsonism and akathisia assessed by incidence of rating scales were higher in the Invega Sustenna 100 mg group (18% and 11%, respectively) than in the Invega Sustenna 50 mg group (9% and 5%, respectively) and placebo group (7% and 4%, respectively).
In the 13-week study in subjects with schizophrenia involving 150 mg initiation dosing, the incidence of any treatment-emergent EPS-related adverse events was similar to that of the placebo group (8%), but exhibited a dose-related pattern with 6%, 10%, and 11% in the Invega Sustenna 150/25 mg, 150/100 mg, and 150/150 mg groups, respectively. Hyperkinesia was the most frequent category of EPS-related adverse events in this study, and was reported at a similar rate between the placebo (4.9%) and Invega Sustenna 150/100 mg (4.8%) and 150/150 mg (5.5%) groups, but at a lower rate in the 150/25 mg group (1.3%). The percentage of subjects who required use of an anticholinergic medication was low and similar across the placebo and paliperidone palmitate groups (11% to 13%).
Table 6: Treatment-Emergent Extrapyramidal Symptoms (EPS)-Related Adverse Events by MedDRA EPS Group Terms in a 13-week 150 mg Initiation Dose Study – Schizophrenia Studies
| Percentage of Subjects | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Invega Sustenna | |||||||||||||
| Placebo | 150/25 mg1 | 150/100 mg1 | 150/150 mg1 | ||||||||||
| EPS Group | (N=164) | (N=160) | (N=165) | (N=163) | |||||||||
| Hyperkinesia2 | 4.9 | 1.3 | 4.8 | 5.5 | |||||||||
| Parkinsonism2 | 1.8 | 3.1 | 3.0 | 4.3 | |||||||||
| Tremor | 2.4 | 0.6 | 1.8 | 1.2 | |||||||||
| Dyskinesia4 | 0.6 | 0 | 1.2 | 0.8 | |||||||||
| Dystonia5 | 0.6 | 1.9 | 0 | 0 |
|---|
- 1. Initial deltoid injection of 150 mg followed by either 25 mg, 100 mg, or 150 mg every 4 weeks by deltoid or gluteal injection. (See 14 CLINICAL TRIALS)
- 2. Hyperkinesia group includes: Akathisia, restless legs syndrome, restlessness
- 3. Parkinsonism group includes: Extrapyramidal disorder, hypertonia, musculoskeletal stiffness, parkinsonism, drooling, masked facies, muscle tightness, hypokinesia
- 4. Dyskinesia group includes: Dyskinesia, choreoathetosis, muscle twitching, myoclonus, tardive dyskinesia
- 5. Dystonia group includes: Dystonia, muscle spasms
In the long-term study in subjects with schizoaffective disorder, the treatment-emergent EPS-related group adverse events reported during the 25-week open-label Invega Sustenna treatment period included hyperkinesia (12.3%), parkinsonism (8.7%), tremor (3.4%), dyskinesia (2.5%), and dystonia (2.1%). During the 15-month double-blind phase, the overall incidence of EPS-related adverse events was similar in the Invega Sustenna and the placebo group (8.5% and 7.1% respectively). The most commonly reported treatment-emergent EPS-related (group term) adverse events (> 2%) in any treatment group in the double-blind phase of the study (Invega Sustenna versus placebo) were hyperkinesia (3.7% vs. 2.9%), parkinsonism (3.0% vs. 1.8%), and tremor (1.2% vs. 2.4%). The symptom scores for the Extrapyramidal Symptom Rating Scale – Abbreviated (ESRS-A) movement severity subscales (parkinsonism, dystonia, dyskinesia, akathisia) were reported as either absent or minimal for the majority of subjects in the open-label and double-blind phases. Treatment with anticholinergic medications for management of EPS-related symptoms was initiated by 13.5% of subjects during the open-label period. During the double-blind period 4.3% and 3.5% of subjects in the Invega Sustenna and placebo groups, respectively, initiated treatment with anticholinergic medications for EPS-related symptoms.
Weight Gain
In the 13-week study in subjects with schizophrenia involving the recommended initiation regimen (i.e., the initial 150 mg and 100 mg deltoid injections), the proportions of subjects with a weight increase from baseline of ≥ 7% were more common among subjects in the Invega Sustenna groups than in the placebo group. The proportion of subjects with an abnormal weight increase ≥ 7% showed a dose-related trend, with a 5% incidence rate in the placebo group compared with rates of 6%, 8%, and 13% in the Invega Sustenna 25 mg, 100 mg, and 150 mg groups, respectively.
In the two 13-week, fixed-dose, double-blind, placebo-controlled trials (pooled data) in subjects with schizophrenia, the proportions of subjects meeting a weight gain criterion of ≥ 7% of body weight were 6%, 9%, and 10% in the Invega Sustenna 25 mg, 50 mg, and 100 mg groups, respectively, compared with 2% in the placebo group. In the 9-week, fixed-dose, double-blind, placebo-controlled trial, 8% and 6% in the Invega Sustenna 50 mg and 100 mg groups, respectively, met this criterion compared with 4% in the placebo group.
During the 33-week open-label transition/maintenance period of the long-term trial in subjects with schizophrenia, 12% of Invega Sustenna-treated subjects met this criterion; the mean weight change from open-label baseline was +0.7 kg. In the variable length double-blind phase, this criterion (weight gain of ≥ 7% from double-blind phase to endpoint) was met by 6% of Invega Sustenna-treated subjects (median duration 171 days [range 1 day - 407 days]) compared with 3% of placebo-treated subjects (median duration 105 days [range 8 days - 441 days]); the mean weight change from double-blind baseline was +0.5 kg for Invega Sustenna compared with -1.0 kg for placebo. Similar results were observed in the open-label extension phase of this study.
During the initial 25-week open-label period of the long-term study in subjects with schizoaffective disorder, Invega Sustenna was associated with a mean change from baseline in weight of +2.2 kg and 18 % of subjects had an increase in body weight of ≥ 7% (n=653). During the 15-month double-blind period of the study, the mean weight change from double-blind baseline was -0.2 kg for the Invega Sustenna group and -0.8 kg for placebo group. An increase in body weight of ≥ 7% was reported for 13% of subjects in the Invega Sustenna group (n=161) compared to 6% of subjects in the placebo group during the double-blind period (n=168).
Pain Assessment and Local Injection Site Reactions
In the 13-week study in subjects with schizophrenia, involving the recommended initiation regimen (i.e., the initial 150 mg and 100 mg deltoid injections), the mean intensity of injection pain reported by subjects using a visual analog scale (0 mm = no pain to 100 mm = unbearably painful) at first injection was 22 and 18 for Invega Sustenna and placebo groups, respectively. Throughout the rest of the study when injections could be administered in either the gluteal or deltoid site, mean pain scores ranged between 10–15 mm for gluteal injections, and from 15–21 mm for deltoid injections. Thus, pain at the deltoid site tended to be greater, although still usually mild. Investigator ratings of pain were consistent with the subject ratings. Although less frequent, there was also more swelling at the deltoid site as compared to the gluteal site.
Overall, occurrences of pain, induration, redness, or swelling, at injection sites, as assessed by blinded study personnel, were infrequent, generally mild, and tended to decrease over time.
Constipation
Patients should be advised of the risk of severe constipation during Invega Sustenna treatment, and they should tell their doctor if constipation occurs or worsens, since they may need medical intervention.
Adverse Events Reported with Oral Paliperidone The following is a list of additional adverse events that have been reported with oral paliperidone:
Cardiac disorders: bundle branch block left, sinus arrhythmia
Eye disorders: dry eye
Gastrointestinal disorders: intestinal obstruction
General disorders and administration site conditions: edema, edema peripheral
Immune system disorders: anaphylactic reaction
Infections and infestations: rhinitis, viral infection, respiratory tract infection
Injury, poisoning and procedural complications: fall
Investigations: blood creatine phosphokinase increased, blood insulin increased, blood pressure increased, electrocardiogram QT corrected interval prolonged, electrocardiogram T wave abnormal, electrocardiogram T wave inversion, heart rate increased, insulin C-peptide increased
Musculoskeletal and connective tissue disorders: musculoskeletal pain, neck pain, shoulder pain, torticollis, trismus
Nervous system disorders: cogwheel rigidity, grand mal convulsion, parkinsonian gait, transient ischemic attack
Psychiatric disorders: aggression, sleep disorder
Reproductive system and breast disorders: breast engorgement, breast enlargement, breast pain, breast tenderness, retrograde ejaculation
Respiratory, thoracic and mediastinal disorders: epistaxis, wheezing, dysphonia, hyperventilation, pneumonia aspiration, pulmonary congestion, respiratory tract congestion
Skin and subcutaneous tissue disorders: rash papular
Vascular disorders: hypotension, ischemia
Adverse Reactions Reported with Risperidone
Paliperidone is the active metabolite of risperidone. Therefore, the adverse reaction profiles of both the oral and injectable formulations of paliperidone are relevant to one another and, also, to risperidone. In addition to the above adverse reactions, the following adverse reactions have been noted with the use of risperidone products and can be expected to occur with both the oral and injectable formulations of paliperidone:
General disorders and administration site conditions (observed with the injectable formulation of risperidone): injection site cyst, injection site necrosis, injection site ulcer
Nervous system disorders: cerebrovascular disorder
Respiratory, thoracic and mediastinal disorders: rales
See also 8.5 Post-Market Adverse Reactions, Safety Information Reported with Risperidone.
8.3 Less Common Clinical Trial Adverse Reactions
The following additional adverse events occurred in < 2% of Invega Sustenna-treated subjects in the above four short-term fixed-dose, double-blind, placebo-controlled trials in subjects with schizophrenia. In addition, the following also includes adverse events reported in Invega Sustenna-treated subjects with schizophrenia at any rate who participated in other trials. All events assessed as possible drug-related adverse events are included. In addition, medically/clinically meaningful events, particularly those that are likely to be useful to the prescriber or that have pharmacologic plausibility, have been included. Although the events reported occurred during treatment with Invega Sustenna they were not necessarily caused by it.
Events are categorized by organ class and listed in order of decreasing frequency according to the following definitions:
Common ≥1/100 to <1/10
Uncommon ≥1/1,000 to <1/100
Rare ≥1/10,000 to <1/1,000
Very rare <1/10,000, including isolated reports
Not known Cannot be estimated from the available data
Blood and lymphatic system disorders: Uncommon: anemia, eosinophil count increased, hematocrit decreased, white blood cell count decreased
Cardiac disorders: Common: bradycardia; Uncommon: atrioventricular block first degree, palpitations, bundle branch block, electrocardiogram abnormal, postural orthostatic tachycardia syndrome, sinus tachycardia
Ear and labyrinth disorders: Uncommon: ear pain, tinnitus, vertigo
Endocrine disorders: Common: hyperprolactinemia; Not known: glucose urine present
Eye disorders: Uncommon: conjunctivitis, oculogyric crisis, vision blurred; Rare: eye movement disorder, eye rolling, glaucoma, lacrimation increased, ocular hyperemia, photophobia
Gastrointestinal disorders: Uncommon: gastroenteritis, salivary hypersecretion; Rare: cheilitis, dysphagia, fecal incontinence, fecaloma, swollen tongue
General disorders and administration site conditions: Uncommon: chest discomfort, face edema, gait abnormal, malaise, thirst; Rare: body temperature decreased, body temperature increased, chills, drug withdrawal syndrome
Hepatobiliary disorders: Common: transaminases increased; Uncommon: Gamma-glutamyltransferase increased, hepatic enzyme increased
Immune system disorders: Uncommon: hypersensitivity
Infections and infestations: Uncommon: acarodermatitis, cellulitis, cystitis, ear infection, eye infection, pneumonia, sinusitis, subcutaneous abscess, tonsilitis; Rare: onychomycosis
Investigations: Common: blood glucose increased, blood triglycerides increased
Metabolism and nutrition disorders: Common: hyperglycemia; Uncommon: anorexia, hyperinsulinemia, increased appetite; Rare: polydypsia
Musculoskeletal and connective tissue disorders: Uncommon: joint stiffness, muscle rigidity, muscle spasms, muscle tightness, muscle twitching; Rare: joint swelling, muscular weakness, nuchal rigidity, posture abnormal, rhabdomyolysis
Nervous system disorders: Common: tremor, dystonia; Uncommon: bradykinesia, convulsion, disturbance in attention, dizziness postural, drooling, dysarthria, hypoesthesia, lethargy, oromandibular dystonia, paresthesia, parkinsonism, psychomotor hyperactivity, syncope, tardive dyskinesia; Rare: balance disorder, cerebrovascular accident, coordination abnormal, depressed level of consciousness, diabetic coma, head intubation, loss of consciousness, neuroleptic malignant syndrome, unresponsive to stimuli
Psychiatric disorders: Uncommon: confusional state, libido decreased, restlessness; Rare: anorgasmia, blunted effect
Renal and urinary disorders: Uncommon: dysuria, pollakiuria, urinary incontinence
Reproductive system and breast disorders: Uncommon: amenorrhea, ejaculation disorder, erectile dysfunction, galactorrhea, gynecomastia, menstrual disorder, menstruation delayed, menstruation irregular, sexual dysfunction, vaginal discharge; Rare: breast discharge, breast discomfort
Skin and subcutaneous tissue disorders: Uncommon: acne, dry skin, eczema, erythema, pruritus generalized, urticaria; Rare: drug eruption, hyperkeratosis, seborrheic dermatitis, skin discolouration
Vascular disorders: Uncommon: orthostatic hypotension; Rare: flushing
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
In the pooled data from the two double-blind, placebo-controlled, 13-week, fixed-dose trials in subjects with schizophrenia, a between-group comparison revealed no medically important differences between Invega Sustenna and placebo in the proportions of subjects experiencing potentially clinically significant changes in routine serum chemistry, hematology, or urinalysis parameters. Similarly, there were no differences between Invega Sustenna and placebo in the incidence of discontinuations due to changes in hematology, urinalysis, or serum chemistry, including mean changes from baseline in fasting glucose, insulin, c-peptide, triglycerides, HDL, LDL, and total cholesterol measurements. However, Invega Sustenna was associated with increases in serum prolactin (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism). Observed increases in serum prolactin concentrations were mostly asymptomatic and infrequently associated with reports of potentially prolactin-related adverse events. The results from the 13-week study involving 150 mg initiation dosing, the 9-week, fixed-dose, double-blind, placebo-controlled trial, and the double-blind phase of the long-term trial in subjects with schizophrenia exhibited comparable findings. In the long term study in subjects with schizoaffective disorder, increases in serum prolactin concentrations were also observed, were mostly asymptomatic and infrequently associated with potentially prolactin-related adverse events.
8.5 Post-Market Adverse Reactions
Adverse events first identified as ADRs during post-marketing experience with paliperidone are included in Table 7. In Table 7, ADRs are presented by frequency category based on spontaneous reporting rates.
Table 7: Adverse Drug Reactions Identified During Post-Marketing Experience with Paliperidone by Frequency Category Estimated from Spontaneous Reporting Rates
| Blood and lymphatic system disorders | |
| Very rare | Thrombocytopenia |
| Cardiac disorders | |
| Very rare | Atrial fibrillation |
| Endocrine disorders | |
| Not known | Inappropriate antidiuretic hormone secretion |
| Eye disorders | |
| Not known | Floppy iris syndrome (intraoperative) |
| Gastrointestinal disorders | |
| Very rare | Pancreatitis |
| Very rare | Ileus |
| General disorders and administration site conditions | |
| Very rare | Hypothermia, Injection site abscess, Injection site cellulitis |
| Hepatobiliary disorders | |
| Not known | Jaundice |
| Immune System Disorders | |
| Rare | Hypersensitivity (including very rare events of angioedema, anaphylaxis, and anaphylactic shock) |
| Metabolism and nutrition disorders | |
| Very rare | Diabetes mellitus, Diabetic ketoacidosis, Hypoglycemia |
| Not known | Water intoxication |
| Nervous system disorders | |
| Very rare | Dysgeusia |
| Pregnancy, puerperium and perinatal conditions | |
| Very rare | Drug withdrawal syndrome neonatal |
| Psychiatric disorders | |
| Very rare | Catatonia, Mania |
| Renal and urinary disorders | |
| Very rare | Urinary retention |
| Reproductive system and breast disorders | |
| Very rare | Priapism |
| Respiratory, thoracic and mediastinal disorders | |
| Very rare | Sleep apnea syndrome |
| Skin and subcutaneous tissue disorders | |
| Rare | Angioedema |
| Very rare | Alopecia |
| Not known | Stevens-Johnson syndrome/Toxic epidermal necrolysis |
| Vascular disorders | |
| Very rare | Deep vein thrombosis, Pulmonary embolism |
In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including paliperidone. Granulocytopenia and agranulocytosis have also been reported (see 7 WARNINGS AND PRECAUTIONS, Hematologic). Agranulocytosis has been reported very rarely during post-marketing surveillance.
Atypical antipsychotic drugs, such as paliperidone, have been associated with cases of sleep apnea, with or without concomitant weight gain. In patients who have a history of, or that are at risk of, sleep apnea, Invega Sustenna should be prescribed with caution.
Risks of somnambulism (sleep walking) and sleep-related eating disorder have been associated with the use of atypical antipsychotics including Invega Sustenna.
Hypersensitivity
There have been very rare spontaneous reports of severe hypersensitivity (e.g., anaphylaxis, angioedema, anaphylactic shock) in some patients after injection with Invega Sustenna. Symptoms of anaphylaxis include skin rash, hives, peripheral edema, swollen eye, tongue and face, hyperhidrosis, dyspnea, and hypotension. It is unknown as to how many of these patients previously tolerated oral risperidone or paliperidone. However, anaphylactic-type reactions have occurred after injection with Invega Sustenna in patients who have previously tolerated oral risperidone or oral paliperidone (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity and 4 DOSAGE AND ADMINISTRATION).
Safety Information Reported with Risperidone
Paliperidone is the major active metabolite of risperidone. The release profile and pharmacokinetic characteristics of Invega Sustenna are considerably different from those observed with oral immediate-release risperidone formulations, as well as those from risperidone long-acting injection (see 10 CLINICAL PHARMACOLOGY); however, the receptor binding profile of paliperidone is very similar to that of the parent compound. Safety information reported with oral risperidone and risperidone long-acting injection in clinical trials and post-marketing experience that may be relevant to Invega Sustenna can be found in local labelling for risperidone, as well as 8.2 Clinical Trial Adverse Reactions, Adverse Reactions Reported with Risperidone.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Since paliperidone palmitate is hydrolyzed to paliperidone (see 10 CLINICAL PHARMACOLOGY), results from studies with oral paliperidone should be taken into consideration when assessing drug-drug interaction potential.
Potential for Invega Sustenna to Affect Other Drugs
Paliperidone is not expected to cause clinically important pharmacokinetic interactions with drugs that are metabolized by cytochrome P450 isozymes. Paliperidone at relevant clinical concentrations had no or only marginal inhibitory effect on the major CYP450s including CYP1A2, CYP2A6, CYP2C8/9/10, CYP2D6, CYP2E1, CYP3A4, and CYP3A5. Therefore, paliperidone is not expected to inhibit clearance of drugs that are metabolized by these metabolic pathways in a clinically relevant manner. Paliperidone is also not expected to have enzyme-inducing properties.
Paliperidone is a weak inhibitor of P-glycoprotein (P-gp) at high concentrations. No in vivo data are available and the clinical relevance of this with respect to P-gp mediated transport of other drugs is unknown.
Potential for Other Drugs to Affect Invega Sustenna
While in vitro studies indicate that CYP3A4 and CYP2D6 may be minimally involved in the paliperidone metabolism there are no indications in vitro nor in vivo that these isozymes play a significant role in the metabolism of paliperidone (see 10.3 Pharmacokinetics, Metabolism and Elimination). Paliperidone was also shown to be a P-glycoprotein substrate but the influence of any drug-drug interaction with P-glycoprotein at the level of the blood-brain barrier is likely to be modest.
The co-administration of oral paliperidone extended-release tablets with carbamazepine, a strong CYP3A4 and P-glycoprotein inducer, resulted in a decrease of 37% in the mean steady-state Cmax and AUC of paliperidone (see 9.4 Drug-Drug Interactions).
A population pharmacokinetic analysis from a study using oral paliperidone extended-release tablets to evaluate the influence of predicted CYP2D6 phenotype on exposure indicated that no adjustment in the paliperidone dose on the basis of predicted phenotype is warranted (see 10.3 Pharmacokinetics).
Paliperidone is not a substrate of CYP1A2, CYP2A6, CYP2C9, CYP2C19, and CYP3A5. This suggests that an interaction with inhibitors or inducers of these isozymes is unlikely.
9.3 Drug-Behavioural Interactions
Smoking
No dosage adjustment is recommended based on smoking status. Based on in vitro studies utilizing human liver enzymes, paliperidone is not a substrate for CYP1A2; smoking, a CYP1A2 inducer, should, therefore, not have an effect on the pharmacokinetics of paliperidone. Consistent with these in vitro results, population pharmacokinetic evaluation has not revealed any statistically significant differences between smokers and non-smokers in an analysis performed with oral paliperidone extended-release tablets.
9.4 Drug-Drug Interactions
No specific drug interaction studies have been performed with Invega Sustenna. The information below is obtained from studies with oral paliperidone.
Carbamazepine and other potent CYP3A4 inducers
Co-administration of oral paliperidone extended-release tablets once daily with carbamazepine 200 mg twice daily caused a decrease of approximately 37% in the mean steady-state Cmax and AUC of paliperidone. As is typical of CYP3A4 inducers, carbamazepine is also a P-glycoprotein (P-gp) inducer. Although in vitro studies have shown that paliperidone is a substrate of both P-gp and CYP3A4, the relative contributions of P-gp and CYP3A4 to changes in the pharmacokinetic parameters are unclear.
On initiation of carbamazepine, the dose of Invega Sustenna should be re-evaluated and increased if necessary. Conversely, on discontinuation of carbamazepine, the dose of Invega Sustenna should be re-evaluated and decreased if necessary. Until more data are available, these recommendations should be extended to other potent CYP3A4 inducers and/or P-glycoprotein up-regulators.
Centrally acting drugs and alcohol
Given the primary CNS effects of paliperidone (see 8 ADVERSE REACTIONS), Invega Sustenna should be used with caution in combination with other centrally acting drugs and alcohol.
Drugs with potential for inducing orthostatic hypotension
Because of its potential for inducing orthostatic hypotension (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular), an additive effect may be observed when Invega Sustenna is administered with other therapeutic agents that have this potential.
Concomitant Use with Furosemide
See 7.1 Special Populations regarding increased mortality in elderly patients with dementia concomitantly receiving furosemide plus risperidone.
Levodopa and other dopamine agonists
Paliperidone may antagonize the effect of levodopa and other dopamine agonists.
Lithium
Pharmacokinetic interaction between lithium and Invega Sustenna is unlikely.
Paroxetine
In an interaction study in healthy subjects in which oral paliperidone extended-release tablets once daily was administered concomitantly with paroxetine, a potent CYP2D6 inhibitor, no clinically relevant effects on the pharmacokinetics of paliperidone were observed.
Concomitant Use of Invega Sustenna with Risperidone or Oral Paliperidone
There are no systematically collected safety data to specifically address concomitant use of Invega Sustenna with risperidone, oral paliperidone, or other antipsychotics. Since paliperidone is the major active metabolite of risperidone, caution should be exercised when Invega Sustenna is co-administered with risperidone or oral paliperidone.
Concomitant use of Invega Sustenna with psychostimulants
The combined use of psychostimulants (e.g. methylphenidate) with paliperidone can lead to the emergence of extrapyramidal symptoms upon change of either or both treatments (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
Concomitant use of Invega Sustenna with other QT-prolonging drugs
Caution is advised when prescribing Invega Sustenna with drugs known to prolong the QT interval (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Trimethoprim
Paliperidone, a cation under physiological pH, is primarily excreted unchanged by the kidneys, approximately half via filtration and half via active secretion. Concomitant administration of trimethoprim, a drug known to inhibit active renal cation drug transport, did not influence the pharmacokinetics of paliperidone.
Valproate
Impact of oral paliperidone on the pharmacokinetics of valproate
Co-administration of oral paliperidone extended-release tablets at steady-state (12 mg once daily) with divalproex sodium extended-release tablets (500 mg to 2000 mg once daily) did not affect the steady-state pharmacokinetics of valproate.
Impact of valproate on the pharmacokinetics of oral paliperidone
Co-administration of a single dose of oral paliperidone extended-release tablets 12 mg with divalproex sodium extended-release tablets (two 500 mg tablets once daily) resulted in an increase of approximately 50% in the Cmax and AUC of paliperidone, likely the result of an increased oral absorption. Since no significant effect on the systemic clearance was observed, a clinically significant interaction would not be expected between divalproex sodium extended-release tablets and Invega Sustenna prolonged-release injectable suspension. This interaction has not been studied with Invega Sustenna.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Paliperidone palmitate is hydrolyzed to paliperidone after injection (see 10.3 Pharmacokinetics). The mechanism of action of paliperidone, as with other drugs having efficacy in schizophrenia and schizoaffective disorder, is unknown. However, it has been proposed that the drug’s therapeutic activity in schizophrenia and schizoaffective disorder is mediated through a combination of dopamine Type 2 (D2) and serotonin Type 2 (5HT2A) receptor antagonism. Antagonism at receptors other than D2 and 5HT2A may explain some of the other effects of paliperidone.
10.2 Pharmacodynamics
Paliperidone is a centrally active dopamine D2 antagonist with predominant serotonergic 5-HT2A antagonistic activity. Paliperidone is also active as an antagonist at α1 and α2 adrenergic receptors and H1 histaminergic receptors. Paliperidone has no affinity for cholinergic muscarinic or β1- and β2-adrenergic receptors. The pharmacological activity of the (+)- and (-)- paliperidone enantiomers is qualitatively and quantitatively similar.
Preclinical Pharmacodynamics
I.m. injected paliperidone palmitate is converted to paliperidone, with minimal systemic exposure to paliperidone palmitate in animals as well as in humans. Systemic effects following i.m. administration of paliperidone palmitate are mediated through paliperidone.
Paliperidone is the major active metabolite of risperidone and is pharmacologically very similar to the parent compound. In a series of standard in vivo pharmacology tests, paliperidone, its enantiomers and risperidone showed similar effects at closely related doses. In vitro, paliperidone and risperidone (1) shared nearly the same binding affinity for 5-HT2A, D2, α1, and α2 receptors, (2) reversed dopamine-induced suppression of PRL release from anterior pituitary cells, and (3) reduced 5-HT-induced human platelet aggregation.
Paliperidone displays approximately 15 times higher affinity towards 5-HT2A receptors when compared with clozapine and approximately 120 times higher affinity compared with haloperidol. The affinity to D2 receptors was about 20 times higher compared to clozapine and only 2 to 3 times lower compared with haloperidol. Paliperidone differed from clozapine and haloperidol by the remarkably shallow slope of its D2 receptor dose occupancy curve.
Similar to risperidone, paliperidone does not interact with cholinergic muscarinic receptors.
Cardiovascular Pharmacology
Paliperidone was devoid of major effects on several electrophysiological parameters in isolated cells and cardiac tissues in vitro, at concentrations matching and slightly exceeding therapeutically achieved plasma levels in man. Paliperidone and risperidone produced similar effects on cardio-hemodynamic parameters. Following administration of paliperidone in awake rats (i.v., s.c.) and dogs (p.o.), and in anesthetized dogs, guinea pigs and rabbits (i.v.) at higher tested dose levels, paliperidone produced cardiovascular effects consisting mainly of increased heart rate, decreased blood pressure, and changes in QT- and PQ-intervals. However, the results from these in vivo studies indicated an absence of cardiac electrophysiological effects, including QTc changes, with paliperidone at doses yielding plasma concentrations slightly in excess of the therapeutic ones in humans.
10.3 Pharmacokinetics
Preclinical Pharmacokinetics
After i.m. administration of paliperidone palmitate, the exposure to the unhydrolyzed prodrug is very low, whereas a prolonged release of paliperidone, with a duration of at least one month, is observed both in humans and all animal species tested. Nonclinical animal models were also used to simulate the consequences of accidental partial intravenous administration or intralipomatous injection. Following i.v. administration, there was no instantaneous release of the entire dose, but a prolonged release of paliperidone. An injection in the subcutaneous fat layer produced a similar profile, but with lower paliperidone plasma concentrations to that observed after i.m. dosing.
After i.m. injection, paliperidone palmitate forms an agglomerate of nanoparticles. There is a dissociation of the product, most likely by hydrolysis, in the muscle cells surrounding this depot. After hydrolysis paliperidone enters the systemic circulation, whereas the palmitate moiety is probably oxidized in the muscle cells.
Paliperidone exhibited species-dependent stereoselectivity in disposition and plasma protein binding. (-)-Paliperidone was more abundant than (+)-paliperidone in plasma of laboratory animals but not in humans. In mice and rats, (+)-paliperidone showed a higher free fraction, while in dogs and humans, the free fraction of (-)-paliperidone was higher than that of (+)-paliperidone.
Paliperidone was shown to distribute to specific brain regions with high density of 5-HT2A- and D2-receptors and to achieve exposure that was in excess of that in plasma. There was no undue tissue retention of paliperidone except in melanin-containing tissues of pigmented rats. The melanin binding of paliperidone was shown to be reversible.
The major biotransformation routes of paliperidone were similar in laboratory animals and in humans. All metabolites identified in the human mass balance study were also observed in at least one laboratory animal species. All the metabolites that were identified following paliperidone administration in humans were also observed following risperidone administration in humans.
Absorption and Distribution
Due to its extremely low water solubility, paliperidone palmitate dissolves slowly after intramuscular injection before being hydrolyzed to paliperidone and absorbed into the systemic circulation. Following a single intramuscular dose, the plasma concentrations of paliperidone gradually rise to reach maximum plasma concentrations at a median Tmax of 13 days. The release of the drug starts as early as day 1 and lasts for as long as 126 days.
Following intramuscular injection of single doses (25 mg–150 mg) in the deltoid muscle, on average, a 28% higher Cmax was observed compared with injection in the gluteal muscle. The two initial deltoid intramuscular injections of 150 mg on day 1 and 100 mg on day 8 help attain therapeutic concentrations rapidly.
This dosing regimen and the release profile of Invega Sustenna results in rapid attainment of sustained therapeutic concentrations similar to the steady state concentrations obtained by monthly dosing at 75 mg. At lower or higher monthly doses of Invega Sustenna, plasma concentrations gradually decrease or increase respectively until steady state for the lower or higher doses is achieved; see
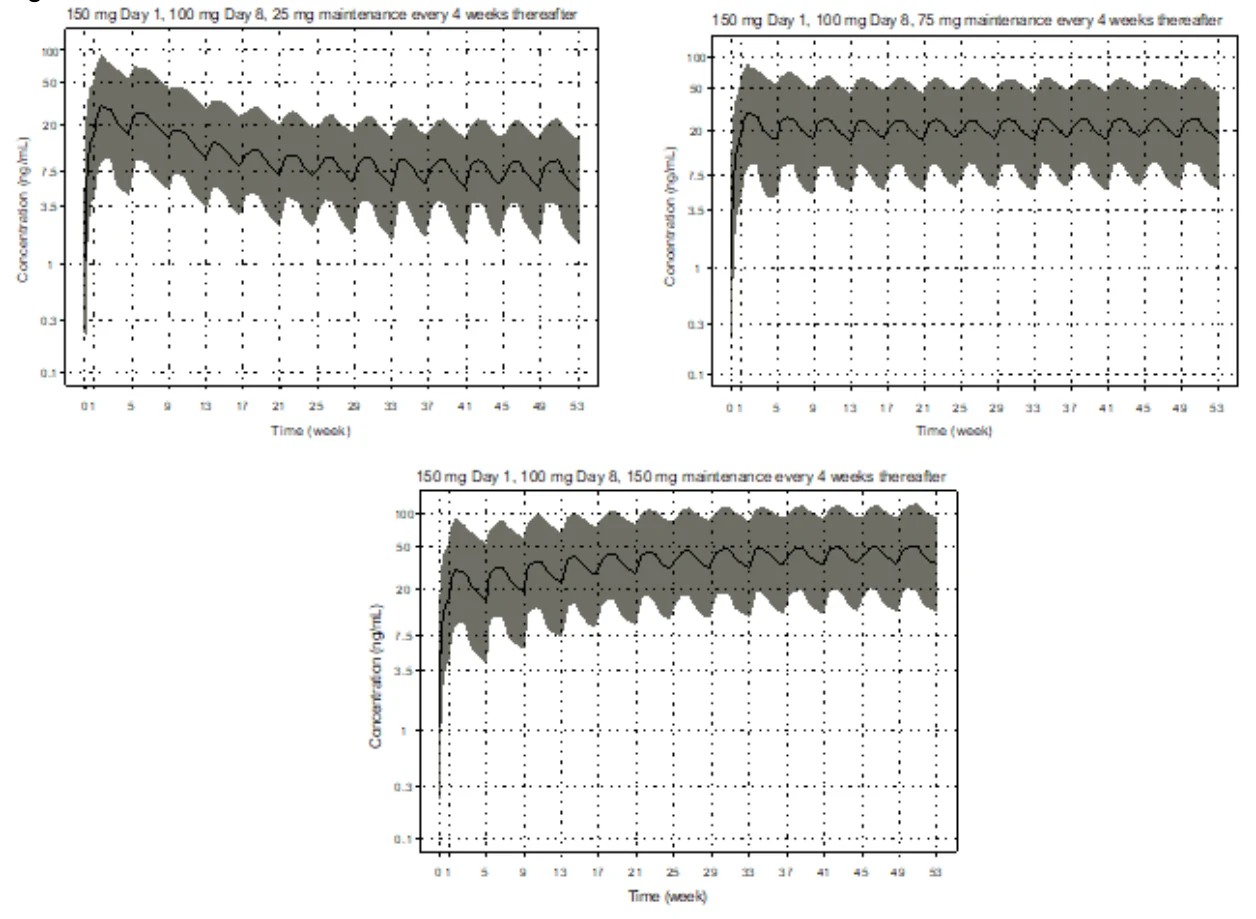
Figure 1.
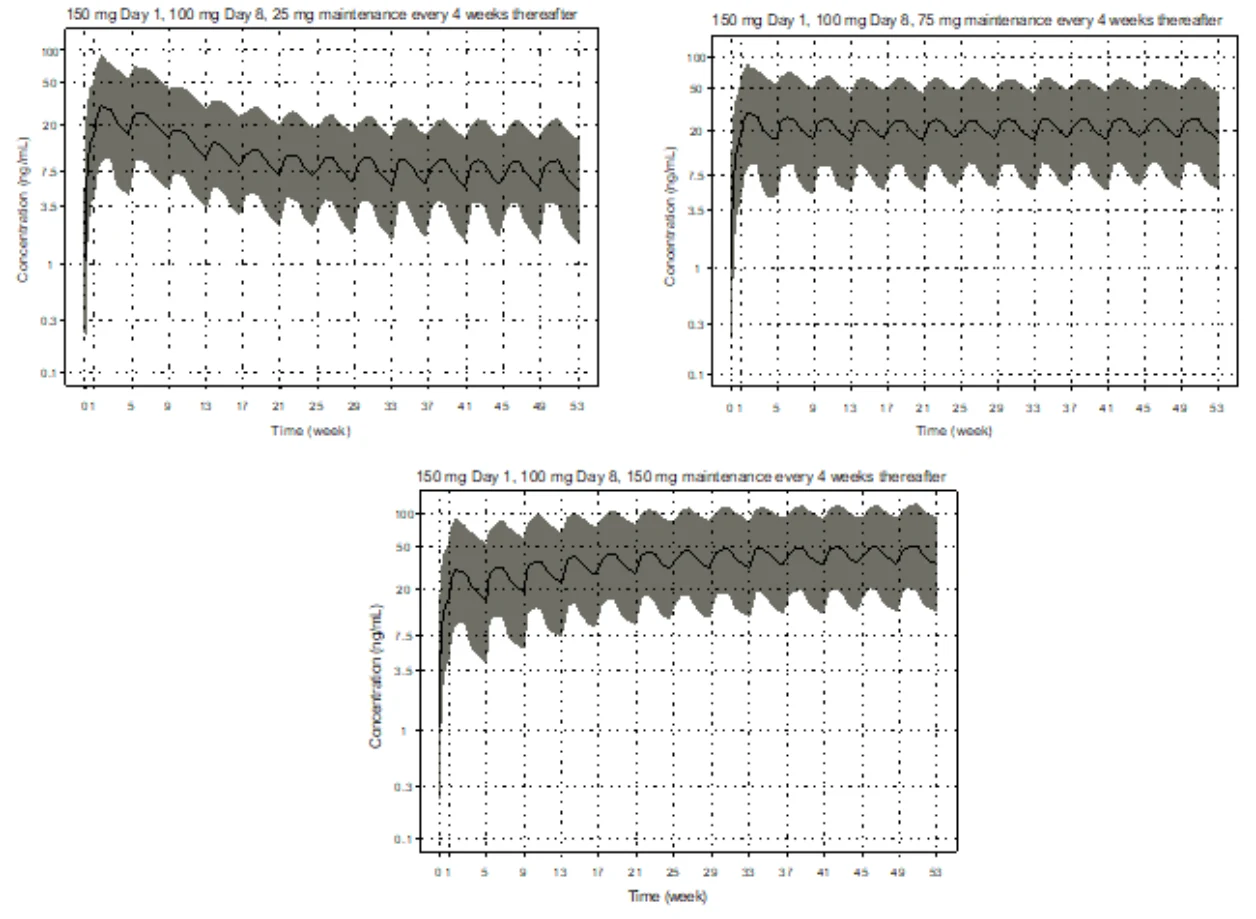
Figure 1: Population PK simulations of plasma paliperidone concentrations with a range of maintenance doses. The solid line and the shaded area represent the median and the 90% prediction interval based on the population PK simulation.
The AUC of paliperidone following Invega Sustenna administration was dose-proportional over a 25 mg–150 mg dose range, and less than dose-proportional for Cmax for doses exceeding 50 mg. The mean steady-state peak: trough ratio for an Invega Sustenna dose of 100 mg was 1.8 following gluteal administration and 2.2 following deltoid administration. The median apparent half-life of paliperidone following Invega Sustenna administration increased over the dose range of 25 mg–150 mg from 25–49 days.
Following administration of paliperidone palmitate the (+) and (-) enantiomers of paliperidone interconvert, reaching an AUC (+) to (-) ratio of approximately 1.6–1.8.
Based on a population analysis, the apparent volume of distribution of paliperidone is 391 L. The plasma protein binding of racemic paliperidone is 74%.
Metabolism and Elimination
The following data are based on a human mass balance study using oral solution of 14C-paliperidone which has approximately 100% bioavailability. One week following administration of a single 1 mg dose of oral solution 14C-paliperidone, 59% of the dose was excreted unchanged into urine, indicating that paliperidone is not extensively metabolized in the liver. Approximately 80% of the administered radioactivity was recovered in urine and 11% in the feces.
Four metabolic pathways have been identified in vivo, none of which accounted for more than 6.5% of the dose: dealkylation, hydroxylation, dehydrogenation, and benzisoxazole scission. Although in vitro studies suggested a role for CYP2D6 and CYP3A4 in the metabolism of paliperidone, there is no evidence in vivo that these isozymes play a significant role in the metabolism of paliperidone. Population pharmacokinetics analyses indicated no discernible difference on the apparent clearance of paliperidone after administration of oral paliperidone between extensive metabolizers and poor metabolizers of CYP2D6 substrates. In vitro studies in human liver microsomes showed that paliperidone does not substantially inhibit the metabolism of medicines metabolized by cytochrome P450 isozymes, including CYP1A2, CYP2A6, CYP2C8/9/10, CYP2D6, CYP2E1, CYP3A4, and CYP3A5.
In vitro studies have shown that paliperidone is a P-gp substrate and a weak inhibitor of P-gp at high concentrations. No in vivo data are available and the clinical relevance is unknown.
Long-Acting Paliperidone Palmitate Injection versus Oral Extended-Release Paliperidone
Invega Sustenna is designed to deliver paliperidone over a monthly period while extended-release oral paliperidone is administered on a daily basis.
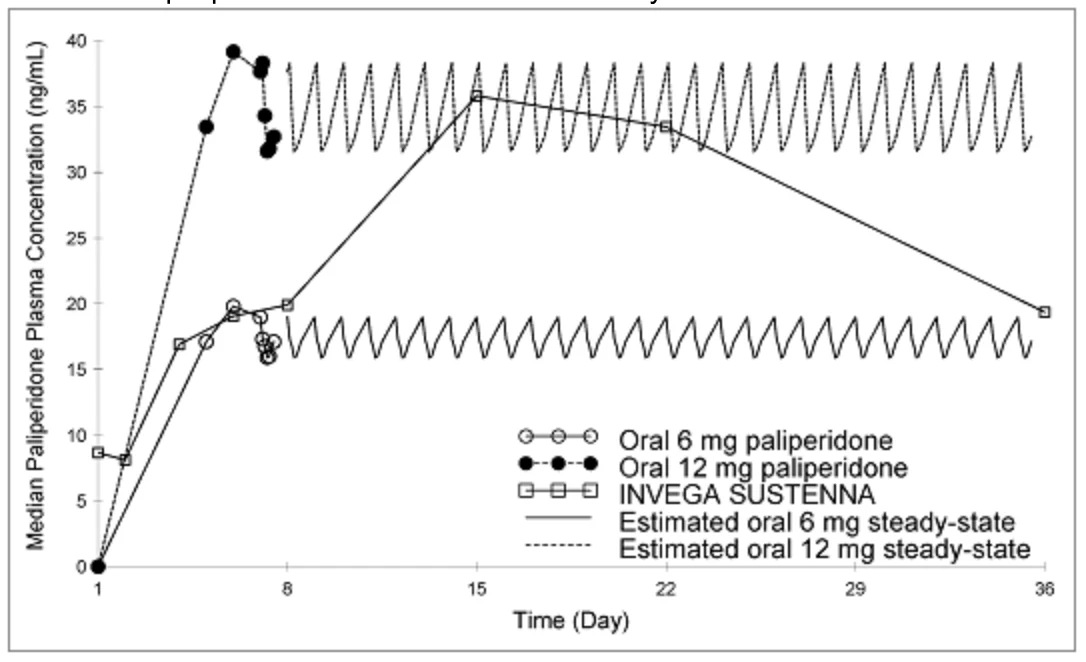
Figure 2 presents the median pharmacokinetic profiles for paliperidone for 5 weeks following Invega Sustenna administration using the recommended initiation regimen compared to the administration of an oral extended-release tablet (6 mg or 12 mg). The initiation regimen for Invega Sustenna (150 mg/100 mg in the deltoid muscle on Day 1/Day 8) was designed to rapidly attain steady-state paliperidone concentrations when initiating therapy without the use of oral supplementation.
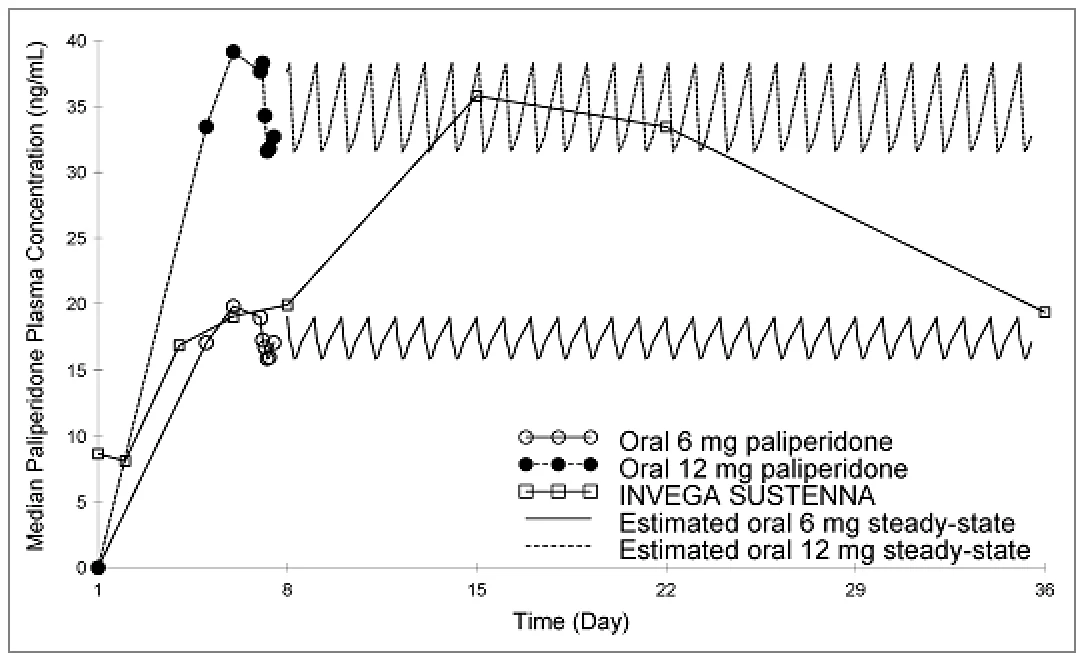
Figure 2: Median plasma concentration-time profiles following median pharmacokinetic profiles for paliperidone for 5 weeks following Invega Sustenna administration using the recommended initiation regimen (initiating with paliperidone palmitate equivalent to paliperidone 150 mg/100 mg in the deltoid muscle on Day 1/Day 8) compared to the daily administration of an oral extended-release tablet (6 mg or 12 mg).
In general, overall initiation plasma levels with Invega Sustenna were within the exposure range observed with 6–12 mg extended-release oral paliperidone. The use of the Invega Sustenna initiation regimen allowed patients to stay in this exposure window of 6–12 mg extended-release oral paliperidone even on trough pre-dose days (Day 8 and Day 36). The intersubject variability for paliperidone pharmacokinetics following delivery from Invega Sustenna was lower relative to the variability determined from extended-release oral paliperidone tablets. Because of the difference in median pharmacokinetic profiles between the two products, caution should be exercised when making a direct comparison of their pharmacokinetic properties
Special Populations and Conditions
- Pediatrics: No data available.
- Geriatrics: No dosage adjustment is recommended based on age alone. However, dose adjustment may be required because of age-related decreases in creatinine clearance (see Renal Insufficiency below and 4 DOSAGE AND ADMINISTRATION).
- Sex: No clinically significant differences were observed between men and women.
- Genetic Polymorphism: Population pharmacokinetics analyses indicated no discernible difference on the apparent clearance of paliperidone after administration of oral paliperidone between extensive metabolizers and poor metabolizers of CYP2D6 substrates.
- Ethnic Origin: Population pharmacokinetics analysis of data from studies with oral paliperidone revealed no evidence of race-related differences in the pharmacokinetics of paliperidone following Invega Sustenna administration.
- Hepatic Insufficiency: Paliperidone is not extensively metabolized in the liver. Although Invega Sustenna was not studied in patients with hepatic impairment, no dose adjustment is required in patients with mild or moderate hepatic impairment. In a study in subjects with moderate hepatic impairment (Child-Pugh class B), the plasma concentrations of unbound paliperidone were similar to those of healthy subjects. No dose adjustment is required in patients with mild to moderate hepatic impairment. Paliperidone has not been studied in patients with severe hepatic impairment.
Renal Insufficiency: Invega Sustenna has not been systematically studied in patients with renal impairment. Based on a limited number of observations with Invega Sustenna in subjects with mild renal impairment and pharmacokinetic simulations, the dose of Invega Sustenna should be reduced in patients with mild renal impairment; Invega Sustenna is not recommended for use in patients with moderate or severe renal impairment (see 4 DOSAGE AND ADMINISTRATION).
The disposition of a single oral dose 3 mg of paliperidone extended-release tablet was studied in subjects with varying degrees of renal function. Elimination of paliperidone decreased with decreasing estimated creatinine clearance. Total clearance of paliperidone was reduced in subjects with impaired renal function by 32% on average in mild (CrCl = 50 to < 80 mL/min), 64% in moderate (CrCl = 30 to < 50 mL/min), and 71% in severe (CrCl = 10 to < 30 mL/min) renal impairment, corresponding to an average increase in exposure (AUCinf) of 1.5-, 2.6-, and 4.8-fold, respectively, compared to healthy subjects. The mean terminal elimination half-life of paliperidone was 24, 40, and 51 hours in subjects with mild, moderate, and severe renal impairment, respectively, compared with 23 hours in subjects with normal renal function (CrCl ≥ 80 mL/min). Paliperidone has not been studied in subjects with creatinine clearance < 10 mL/min.
11 STORAGE, STABILITY AND DISPOSAL
Invega Sustenna should be stored at room temperature (15–30ºC).
Keep out of the reach and sight of children.
Dispose of the syringe, needle and any unused needles in an approved sharps container.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
INVEGA SUSTENNA® (paliperidone palmitate prolonged-release injectable suspension) is an atypical antipsychotic medication containing a racemic mixture of the active ingredient, paliperidone palmitate. After injection, paliperidone palmitate is hydrolyzed to paliperidone (see 10.3 Pharmacokinetics). Paliperidone is a psychotropic agent belonging to the chemical class of benzisoxazole derivatives.
| Proper name | Paliperidone palmitate (prodrug) | Paliperidone (active moiety) |
|---|---|---|
| Chemical name | (±)-3-[2-[4-(6-fluoro-1,2-benzisoxazol-3-yl)-1-piperidinyl]ethyl]-6,7,8,9-tetrahydro-2-methyl-4-oxo-4H-pyrido[1,2-a]pyrimidin-9-yl hexadecanoate | (±)-3-[2-[4-(6-fluoro-1,2-benzisoxazol-3-yl)-1-piperidinyl]ethyl]-6,7,8,9-tetrahydro-9-hydroxy-2-methyl-4H-pyrido[1,2-a]pyrimidin-4-one |
| Molecular formula | C39H57FN4O4 | C23H27FN4O3 |
| Molecular mass | 664.8 | 426.49 |
| Structural formula | 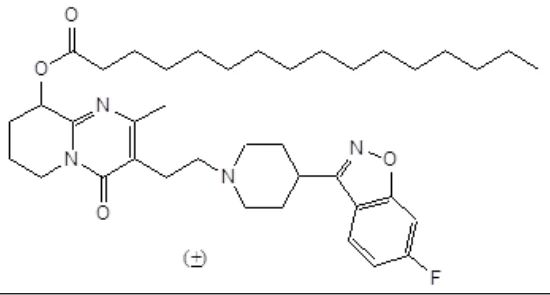 | 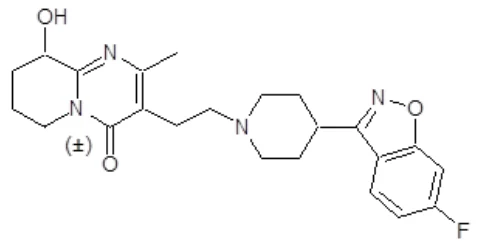 |
| Physical Appearance | Paliperidone palmitate is a white to almost white powder. | Paliperidone is a white to yellow powder. |
| Dissociation Constants | pKa1 = 8.3 (piperidone moiety) pKa2 < 3 (pyrimidine moiety) | pKa1 = 8.2 (piperidone moiety) pKa2 = 2.6 (pyrimidine moiety) |
| Partition Coefficients | log p > 5 | log p = 2.39 |
| Solubility | Paliperidone palmitate is insoluble in 0.1N HCl, 0.1N NaOH, and water; very slightly soluble in ethanol, methanol, and 2-propanol; freely soluble in dichloromethane. | Paliperidone is sparingly soluble in 0.1N HCl and methylene chloride; practically insoluble in water, 0.1N NaOH, and hexane; and slightly soluble in N,N-dimethylformamide. |
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
Schizophrenia
Studies PSY-3003/3004/3007: Trial Design and Study Demographics
The efficacy of Invega Sustenna in the treatment of schizophrenia was established in three 13-week double-blind, randomized, placebo-controlled, fixed-dose studies of acutely relapsed adult patients who met DSM-IV criteria for schizophrenia. The fixed doses of Invega Sustenna in these studies were given on days 1, 8, 36, and 64 of these studies, i.e., at a weekly interval for the initial two doses and then every 4 weeks for maintenance.
Efficacy was evaluated using the Positive and Negative Syndrome Scale (PANSS) and the Clinical Global Impression-Severity (CGI-S) Scale.
Studies PSY-3003/3004/3007: Study Results
Study PSY-3007
In a 13-week study (n=636) comparing three fixed doses of Invega Sustenna (initial deltoid injection of 150 mg followed by 3 gluteal or deltoid doses of either 25 mg/4 weeks, 100 mg/4 weeks or 150 mg/4 weeks) to placebo, all three doses of Invega Sustenna were superior to placebo in improving the PANSS total score. Based on the ITT LOCF analysis of the primary efficacy variable, PANSS total score, the improvement in all 3 Invega Sustenna dose groups reached statistical significance (25 mg: p=0.034; 100 mg: p<0.001: 150 mg: p<0.001). The 100 mg and 150 mg doses were superior to placebo on the CGI-S scale (p=0.005 and p<0.001 respectively) but not the 25 mg dose.
Study PSY-3003
In another 13-week study (n=349) comparing three fixed doses of Invega Sustenna (50 mg/4 weeks, 100 mg/4 weeks, and 150 mg/4 weeks) to placebo, only 100 mg/4 weeks of Invega Sustenna was superior to placebo in improving the PANSS total score (p=0.019). The 50 mg dose group was numerically superior to placebo, but the difference was not statistically significant. The 100 mg dose was superior to placebo on the CGI-S scale (p=0.010). Although a 150 mg dosage arm was included in this study, due to a medication allocation error affecting this arm only there were insufficient numbers of subjects receiving this dose to allow definitive conclusions concerning the efficacy of this dose.
Study PSY-3004
In a third 13-week study (n=513) comparing three fixed doses of Invega Sustenna (25 mg/4 weeks, 50 mg/4 weeks, and 100 mg/4 weeks) to placebo, all three doses of Invega Sustenna were superior to placebo in improving the PANSS total score (25 mg: p=0.015; 50 mg: p=0.017; 100 mg: p<0.001. All doses were superior to placebo on the CGI-S scale (25 mg: p=0.003; 50 mg: p=0.006; 100 mg: p=0.002).
Studies PSY-3003/3004
In a pooled analysis of the latter two 13-week studies, all paliperidone palmitate groups (25 mg, 50 mg and 100 mg) were statistically significantly superior to placebo for the mean change from baseline to endpoint in the PANSS total score (p≤0.009). The least squares mean difference from placebo ranged from –4.9 to –8.2 in the paliperidone palmitate groups, with the greatest difference in the highest dose group (i.e., 100 mg group).
Study PSY-3001: Trial Design and Study Demographics
The efficacy of Invega Sustenna in maintaining symptomatic control and delaying relapse of schizophrenia was established in a longer-term, double-blind, placebo-controlled, flexible-dose study involving 849 non-elderly adult subjects who met DSM-IV criteria for schizophrenia. This study included a 33-week open-label acute treatment and stabilization phase, a randomized, placebo-controlled phase to observe for relapse and a 52-week open-label extension period. In this study, doses of Invega Sustenna included 25, 50, 75 and 100 mg administered monthly; the 75 mg dose was allowed only in the 52-week open-label extension. Subjects initially received flexible doses (25 – 100 mg) of Invega Sustenna during a 9-week transition period. In order to enter the 24-week maintenance period, subjects were required to have a PANSS score of ≤ 75. Dosing adjustments were only allowed in the first 12 weeks of the maintenance period. During the variable length double-blind phase, patients were randomized to either the same dose of Invega Sustenna (median duration 171 days [range 1 day - 407 days]) they received during the stabilization phase administered every 4 weeks, or to placebo (median duration 105 days [range 8 days - 441 days]). A total of 410 stabilized patients were randomized to either Invega Sustenna or to placebo until they experienced a “relapse” of schizophrenia symptoms. “Relapse” was pre-defined as time to first emergence of one or more of the following: psychiatric hospitalization, ≥ 25% increase (if the baseline score was > 40) or a 10-point increase (if the baseline score was ≤ 40) in total PANSS score on two consecutive assessments, deliberate self-injury, violent behaviour, suicidal/homicidal ideation, or a score of ≥5 (if the maximum baseline score was ≤ 3) or ≥ 6 (if the maximum baseline score was 4) on two consecutive assessments of the individual PANSS items P1 (Delusions), P2 (Conceptual disorganization), P3 (Hallucinatory behaviour), P6 (Suspiciousness/persecution), P7 (Hostility), or G8 (Uncooperativeness). The primary efficacy variable was time to “relapse”.
Study PSY-3001: Study Results
A pre-planned interim analysis (after 68 recurrence events occurred) showed a significantly longer time to “relapse” in patients treated with Invega Sustenna compared to placebo (Figure 3), and the study was stopped early because maintenance of efficacy was demonstrated.
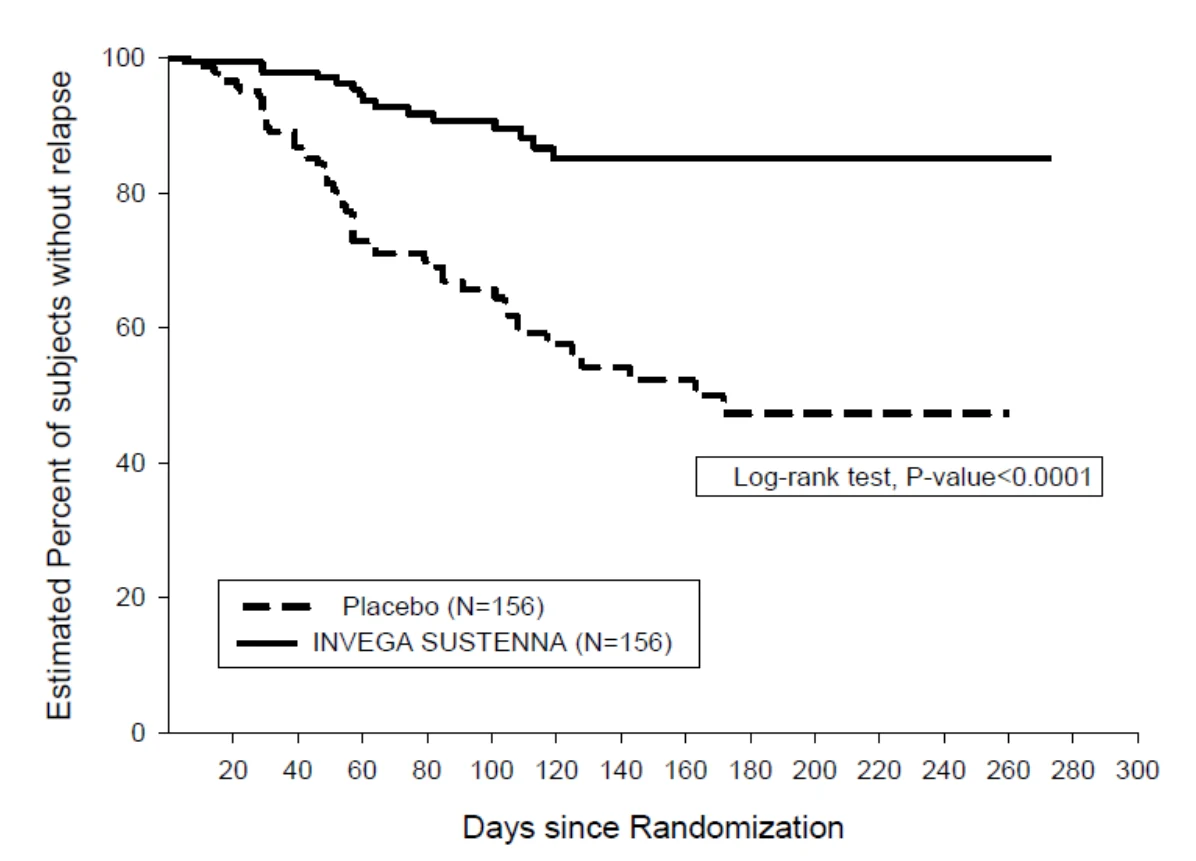
Figure 3: Kaplan-Meier Plot of Time to “Relapse” (Interim Analysis): Intent-to-Treat Analysis Set
The results of the analysis based on the final data, including all data up to the date of the study termination, was consistent with that of the primary efficacy analysis based on the interim data.
An examination of population subgroups did not reveal any clinically significant differences in responsiveness on the basis of gender, age, or race.
Schizoaffective Disorder
Study SCA-3004: Trial Design and Study Demographics
The efficacy of Invega Sustenna in maintaining symptomatic control in subjects with schizoaffective disorder was established in a long-term double-blind, placebo-controlled study involving non-elderly adult subjects who met DSM-IV criteria for schizoaffective disorder, as confirmed by the Structured Clinical Interview for DSM-IV Disorders. Subjects included in the study had 1) acute exacerbation of psychotic symptoms; 2) score ≥4 on ≥3 PANSS items of delusions, conceptual disorganization, hallucinatory behavior, excitement, suspiciousness/persecution, hostility, uncooperativeness, tension, and poor impulse control; and 3) prominent mood symptoms ≥16 on the Young Mania Rating Scale (YMRS) and/or the Hamilton Rating Scale for Depression, 21 item version (HAM D-21). The population included subjects with schizoaffective bipolar and depressive types.
The study included a 13-week, open-label, flexible-dose lead-in period, a 12-week, open-label, fixed dose stabilization period and a randomized, double-blind, placebo controlled, fixed dose period to observe for relapse for up to 15 months. Throughout the study Invega Sustenna 50 mg, 75 mg, 100 mg or 150 mg was administered every 4 weeks as monotherapy or as an adjunct to ongoing stable doses of antidepressant or mood stabilizers. During the 13-week open-label lead-in period subjects received flexible doses of Invega Sustenna (50 mg – 150 mg). Subjects who met stabilization criteria (PANSS total score ≤70, YMRS ≤12, and HAM-D-21 ≤12) at the end of the lead-in period were eligible to continue treatment in the 12-week open-label fixed-dose stabilization period at the same dose of Invega Sustenna they were stabilized on in the lead-in period. Subjects that continued to meet stabilization criteria for 12 consecutive weeks were randomized (1:1) in the double-blind period for up to 15 months of treatment with either the same dose of Invega Sustenna or placebo.
The primary efficacy endpoint during the double-blind period was the time to relapse of symptoms of schizoaffective disorder. Relapse was defined as the first occurrence of one or more of the following: 1) psychiatric hospitalization; 2) intervention employed to avert hospitalization; 3) clinically significant self-injury, suicidal or homicidal ideation or violent behavior; 4) a score of ≥6 (if the score was ≤4 at randomization) of any of the individual PANSS items: delusions, conceptual disorganization, hallucinatory behavior, excitement, suspiciousness/persecution, hostility, uncooperativeness, or poor impulse control; 5) on two consecutive assessments within 7 days: ≥25% increase (if the score at randomization was >45) or ≥10-point increase (if the score at randomization was ≤45) in total PANSS score; a score of ≥5 (if the score was ≤3 at randomization) of any of the individual PANSS items: delusions, conceptual disorganization, hallucinatory behavior, excitement, suspiciousness/persecution, hostility, uncooperativeness, or poor impulse control; an increase of ≥2 points (if the score was 1 [not ill] to 3 [mildly ill] at randomization) or increase of ≥1 point (if the score was ≥4 [moderately ill or worse] at randomization) in CGI-S-SCA overall score.
A total of 667 subjects were enrolled in the study. After the first 13 weeks of open-label, flexible dose Invega Sustenna, 432 subjects met the stabilization criteria. A total of 334 subjects who continued to meet stabilization criteria for an additional 12 consecutive weeks, while receiving open-label fixed dose Invega Sustenna, were randomized in the double-blind, maintenance period for evaluation of relapse. For the 164 subjects who were randomized to Invega Sustenna, dose distribution was 50 mg (4.9%), 75 mg (9.8%), 100 mg (47.0%), and 150 mg (38.4%). Study medication was administered as monotherapy to 45% of subjects and as an adjunct to mood stabilizers or antidepressants to 55% of subjects during the double-blind period. The most commonly used mood stabilizers were lithium and valproate and the most commonly used antidepressants were SSRIs and SNRIs.
Study SCA-3004: Study Results
The time to relapse was statistically significantly longer (p<0.001) for subjects treated with Invega Sustenna compared to placebo (Figure 4). The percentage of subjects meeting relapse criteria was statistically significantly lower in the Invega Sustenna group (15.2%) than in the placebo group (33.5%). The risk (hazard) of relapse of schizoaffective symptoms was 2.49 times greater in the placebo group compared to the Invega Sustenna group. Relapse due to psychotic, manic, depressive and mixed symptoms were reported in both treatment groups, all at higher rates in the subjects that received placebo compared to the subjects that received Invega Sustenna.
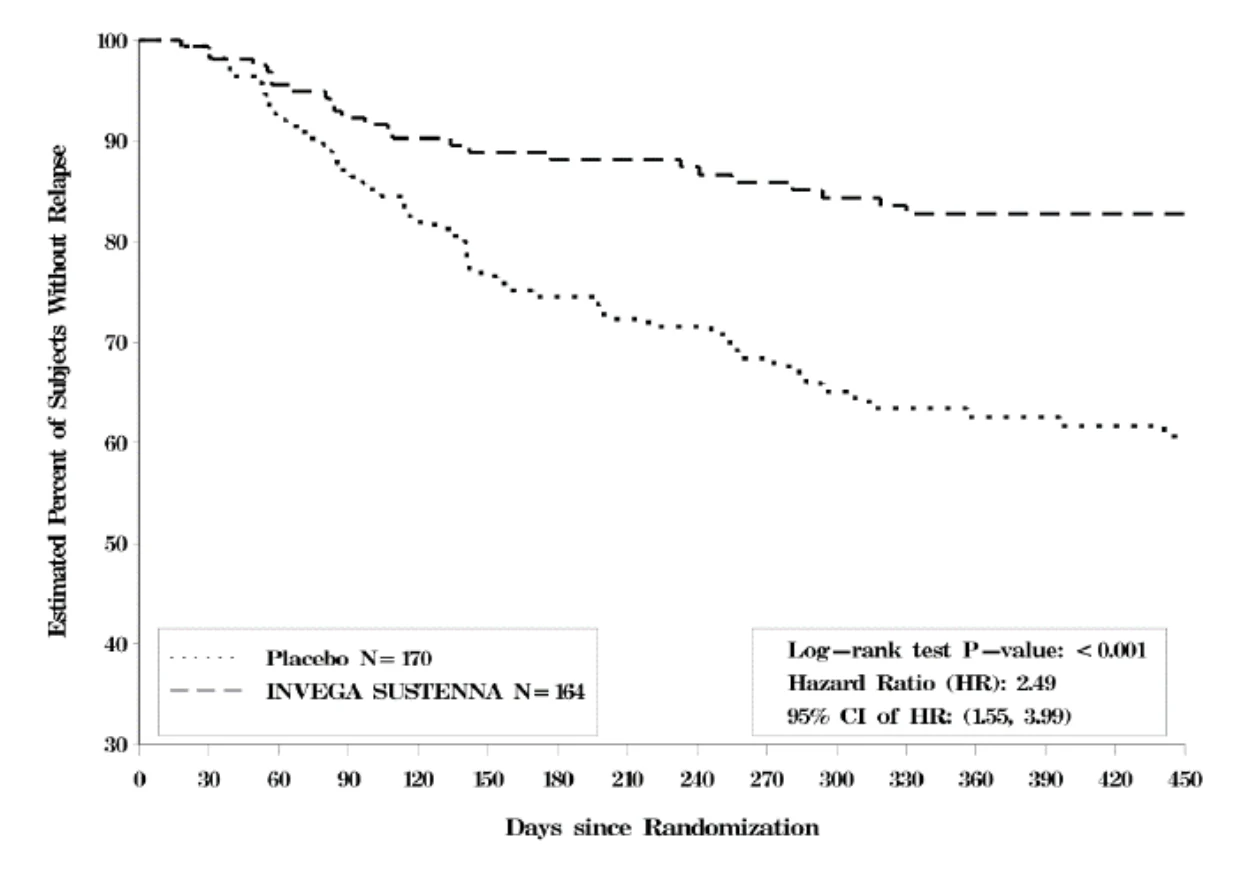
Figure 4: Kaplan-Meier Plot of Estimated Time to Relapse (DB ITT Analysis Set)
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Paliperidone palmitate and paliperidone were tested in an extensive series of toxicity studies. At equal dose levels, the toxicity profile of paliperidone was similar to risperidone in comparative repeat-dose toxicity studies in mice, rats and dogs. The systemic toxicity profile of paliperidone palmitate and paliperidone mainly consisted of findings related to exaggerated pharmacodynamic effects of CNS- and PRL-mediated actions.
In the repeat-dose toxicity studies with paliperidone palmitate, NOAELs could not be established due to injection site tolerability issues which in the animal studies occurred at all dose levels. This poor injection site tolerability does not translate to humans.
In the repeat-dose toxicity studies with paliperidone, NOELs could not be established because signs of exaggerated pharmacology were evident at the lowest dose tested; however, NOAELS were established. Exposure-based safety margins generally were low compared to the systemic exposure at the maximum recommended human dose. However, the main toxicity findings are either species-specific or can be easily assessed in the clinic.
Genotoxicity: Genotoxicity studies were negative.
Carcinogenicity: The carcinogenic potential of paliperidone, an active metabolite of risperidone, was assessed based on studies with risperidone conducted in mice and rats. There were statistically significant increases in pituitary gland adenomas, endocrine pancreas adenomas, and mammary gland adenocarcinomas. These findings are considered to be of little predictive value to humans.
The carcinogenic potential of intramuscularly injected paliperidone palmitate was assessed in rats. There was an increase in mammary gland adenocarcinomas in female rats at 10, 30, and 60 mg/kg/month, which is 0.5, 2, and 4 times, respectively, the maximum recommended human 150 mg dose of Invega Sustenna on a mg/m2 basis. A no-effect dose was not established. Male rats showed an increase in mammary gland adenomas, fibroadenomas, and carcinomas at 30 and 60 mg/kg/month. These findings are considered to be of little relevance in terms of human risk.
Reproductive and Developmental Toxicology: Slight pre-implantation loss was noted at the highest dose level (2.5 mg/kg/day for 21 days) in the female fertility study conducted with paliperidone. The estimated exposure at the embryo-fetal NOEL in this study is similar to that attained in humans and the maximum recommended human dose. Since the increase in pre-implantation loss only occurred in the presence of maternal toxicity, this effect is of little relevance in terms of human risk.
The embryo-fetal developmental toxicity study with paliperidone in rabbits showed slight post-implantation loss at the highest dose level (5 mg/kg/day). The embryo-fetal NOAEL in this study yielded systemic exposure 22- to 34-fold higher than in humans at the maximum recommended human dose. These findings are considered to be of little relevance in terms of human risk.
Juvenile Toxicity: In a 7-week juvenile toxicity study in rats with oral doses of paliperidone of 0.16, 0.63, and 2.5 mg/kg/day, which are 0.12, 0.5, and 1.8 times maximum human oral exposure of 12 mg/day in adolescents on a mg/m2 basis, CNS clinical signs and increased serum prolactin levels in both sexes and pseudopregnancy in females were evident at all dose levels, however no effects on growth, sexual maturation, and reproductive performance were observed after cessation of treatment. Oral doses up to 2.5 mg/kg/day did not generally affect neurobehavioral development in males and females, except for an impairment of learning and memory in female rats treated at 2.5 mg/kg/day and thus there was no safety margin. This effect was not observed on repeated daily testing after discontinuation of treatment.
In a 40-week study in juvenile dogs treated with oral risperidone (which is extensively converted to paliperidone) at doses of 0, 0.31, 1.25, and 5 mg/kg/day, sexual maturation was arrested/delayed at all dose levels, but showed evidence of recovery after discontinuation of treatment in both sexes at 0.31 and 1.25 mg/kg/day and males at 5 mg/kg/day. Effects seen include increased serum prolactin levels in both sexes presumably due to dopamine receptor antagonist activity of risperidone; decreased plasma testosterone levels and sperm counts in males; plasma progesterone undetectable, absence of estrus cycling, low ovary and uterus/cervix weights, absence of active mammary gland development, prominent luteal cells in the ovaries, and endometrial gland hyperplasia in the uterus in females. Reduced body weight gain at all dose levels correlated with reduced long bone growth at 1.25 and 5 mg/kg; however all effects were reversible and 0.31 mg/kg was a NOAEL. Mainly CNS-related clinical signs and increased heart rate at all dose levels were transient and/or reversible.