


Product Monograph - Solufy
Recent Major Label Changes
| 2 Contraindications | 2026-06 |
|---|---|
| 4.1 Dosing Considerations | 2026-06 |
| 7 Warnings and Precautions, Endocrine and Metabolism | 2026-06 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
Part 1: Healthcare Professional Information ............................................................................ 5
- 1.
Indications ........................................................................................................................ 5
1.1. Pediatrics ................................................................................................................... 5
1.2. Geriatrics ................................................................................................................... 6
- 2. Contraindications ............................................................................................................. 6
- 3. Serious Warnings and Precautions Box ............................................................................. 6
- 4.
Dosage and Administration .............................................................................................. 6
4.1. Dosing Considerations ............................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment .......................................................... 7
4.4. Administration ........................................................................................................... 9
4.5. Missed Dose .............................................................................................................. 9
- 5. Overdose ........................................................................................................................ 10
- 6. Dosage Forms, Strengths, Composition, and Packaging .................................................. 11
- 7.
Warnings and Precautions .............................................................................................. 11
General ................................................................................................................................ 11
Carcinogenesis and Genotoxicity ....................................................................................... 111
Cardiovascular ................................................................................................................... 111
Dependence, Tolerance and/or Abuse Liability ................................................................... 11
Driving and Operating Machinery ........................................................................................ 12
Endocrine and Metabolism .................................................................................................. 12
Genitourinary ...................................................................................................................... 14
Hematologic ........................................................................................................................ 14
Monitoring and Laboratory Tests ............................................ Error! Bookmark not defined.
Neurologic ........................................................................................................................... 15
Psychiatric ............................................................................................................................ 17
Skin……… .............................................................................................................................. 17
7.1. Special Populations ................................................................................................. 18
7.1.1. Pregnancy ........................................................................................................ 18
7.1.2. Breastfeeding .................................................................................................. 18
7.1.3. Pediatrics ......................................................................................................... 18
7.1.4. Geriatrics ......................................................................................................... 19
- 8.
Adverse Reactions .......................................................................................................... 20
8.1. Adverse Reaction Overview ..................................................................................... 20
8.2. Clinical Trial Adverse Reactions ............................................................................... 21
8.2.1. Clinical Trial Adverse Reactions – Pediatrics ................................................... 41
8.3. Less Common Clinical Trial Adverse Reactions ........................................................ 44
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ................................................................................................................ 44
8.5. Post-Market Adverse Reactions .............................................................................. 45
- 9.
Drug Interactions ............................................................................................................ 47
9.2. Drug Interactions Overview ..................................................................................... 47
9.3. Drug-Behaviour Interactions ................................................................................... 47
9.4. Drug-Drug Interactions ............................................................................................ 47
9.5. Drug-Food Interactions............................................................................................ 51
9.6. Drug-Herb Interactions ............................................................................................ 51
9.7. Drug-Laboratory Test Interactions .......................................................................... 51
- 10.
Clinical Pharmacology .................................................................................................... 51
10.1. Mechanism of Action ............................................................................................... 51
10.2. Pharmacodynamics ................................................................................................. 52
10.3. Pharmacokinetics .................................................................................................... 52
- 11. Storage, Stability, and Disposal ....................................................................................... 54
Part 2: Scientific Information ................................................................................................. 55
- 13. Pharmaceutical Information ........................................................................................... 55
- 14.
Clinical Trials ................................................................................................................... 55
14.1. Clinical Trials by Indication ...................................................................................... 55
Schizophrenia……………………………………………………………………………………………………………………55
Bipolar I Disorder………………………………………………………………………………………………………………57
Adjunctive Treatment of Major Depressive Disorder (MDD)……………………………………………. 59
14.2. Comparative Bioavailability Studies ........................................................................ 60
- 15. Microbiology .................................................................................................................. 61
- 16. Non-Clinical Toxicology ................................................................................................... 61
- 17. Supporting Product Monographs .................................................................................... 71
Patient Medication Information ............................................................................................ 72
Part 1: Healthcare Professional Information
1. Indications
SOLUFY (Aripiprazole oral solution) is indicated for:
the treatment of schizophrenia and related psychotic disorders in adults.
In controlled clinical trials, aripiprazole was found to improve both positive and negative symptoms. Aripiprazole has been shown to be more effective than placebo in maintaining clinical improvement for up to 26 weeks in adults (see 14.1 Clinical Trials by Indication, Schizophrenia, Adults).
the treatment of manic or mixed episodes in bipolar I disorder in adults.
SOLUFY may be used as acute monotherapy or cotherapy with lithium or divalproex sodium when there is an insufficient acute response to these agents alone. Aripiprazole as cotherapy with lithium or divalproex sodium has been shown to be more effective than placebo plus mood stabilizer in maintaining clinical improvement for up to 1 year in adult patients with manic or mixed episodes associated with bipolar I disorder (see 14.1 Clinical Trials by Indication, Bipolar I Disorder, Adults).
use as an adjunct to antidepressants for the treatment of Major Depressive Disorder (MDD) in adult patients who had an inadequate response to prior antidepressant treatments during the current episode (see 4.1 Dosing Considerations and 14.1 Clinical Trials by Indication, Adjunctive Treatment of Major Depressive Disorder, Adults).
Clinical trials evaluating aripiprazole in MDD did not include aripiprazole monotherapy treatment arms. It is therefore unknown whether efficacy in adjunct treatment is due to aripiprazole alone or from combined treatment with an antidepressant.
1.1. Pediatrics
Pediatrics (< 18 years of age):
SOLUFY is indicated for:
the treatment of schizophrenia in adolescents 15-17 years of age.
Safety and efficacy were evaluated in one 6-week clinical trial in adolescents 13-17 years of age with schizophrenia. Aripiprazole is not indicated for the treatment of schizophrenia in adolescents less than 15 years of age due to insufficient safety and efficacy data (see 8 Adverse Reactions and 14.1 Clinical Trials by Indication, Schizophrenia, Adolescents).
the acute treatment of manic or mixed episodes in bipolar I disorder as monotherapy in adolescents 13-17 years of age.
Safety and efficacy were evaluated in one 4-week clinical trial in pediatric and adolescent patients 10-17 years of age in a current manic or mixed episode as part of bipolar I disorder. Aripiprazole is not indicated for the treatment of manic or mixed episodes in bipolar I disorder in pediatric patients less than 13 years of age due to insufficient safety and efficacy data (see 8
Adverse Reactions and 14.1 Clinical Trials by Indication, Bipolar I Disorder, Pediatric and Adolescent).
SOLUFY should only be prescribed to adolescents with schizophrenia or bipolar I disorder by clinicians who are experienced in the diagnosis and treatment of adolescents with psychiatric illness (see also 4.1 Dosing Considerations).
The safety and efficacy of aripiprazole for the treatment of MDD in patients under the age of 18 years have not been established and its use is not recommended (see 7.1.3 Pediatrics).
1.2. Geriatrics
Geriatrics (≥ 65 years of age): SOLUFY is not indicated in geriatric patients with dementia (see 3 Serious Warnings and Precautions Box and 7.1.4 Geriatrics. The safety and efficacy of aripiprazole in patients 65 years of age or older has not been established. Caution should be used when treating geriatric patients. (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
2. Contraindications
SOLUFY (aripiprazole) is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including non-medicinal ingredients methylparaben and propylparaben or any other non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
Because it contains parabens, SOLUFY should also be avoided in patients with a history of allergic reactions to medicinal products of the PABA ester group, such as ester-type local anesthetics.
3. Serious Warnings and Precautions Box
Increased Mortality in Geriatric Patients with Dementia
Geriatric patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. (see 7.1.4 Geriatrics). SOLUFY is not approved for use in geriatric patients with dementia.
4. Dosage and Administration
4.1. Dosing Considerations
When considering the use of SOLUFY for the treatment of schizophrenia or bipolar I disorder in adolescents or as adjunctive treatment of MDD in adults, clinicians must take into account the safety concerns associated with antipsychotic drugs, a class of drugs to which SOLUFY belongs. Safety concerns of this class include: weight gain, hyperlipidemia, hyperglycemia, and extrapyramidal effects which can be more frequent or more severe in adolescents than in adults. Other safety concerns associated with antipsychotic drugs include tardive dyskinesia and neuroleptic malignant syndrome. Some of these adverse events appear to be dose related (7 Warnings and Precautions, Endocrine and Metabolism, 7 Warnings and Precautions, Neurologic, 8.2 Clinical Trial Adverse Reactions and 8.2.1 Clinical Trial Adverse Reactions - Pediatrics). SOLUFY
- should only be prescribed by clinicians who are aware of the importance and are experienced in the early detection and management of the safety issues associated with this class of drugs.
- The oral solution and tablets can be interchanged on a mg-per-mg basis.
- Enhanced monitoring is recommended when switching formulations for patients stable at the highest dose as other aripiprazole oral solution drug products have shown higher exposure at the 30 mg dose. The comparative bioavailability of doses other than 10 mg was not tested for SOLUFY (10.3 Pharmacokinetics, Absorption; 14.2 Comparative Bioavailability Studies).
- The efficacy and safety of aripiprazole, at doses greater than 30 mg / day, have not been established.
SOLUFY contains fructose and sucrose (see 6 Dosage Forms, Strengths, Composition, and Packaging). SOLUFY should not be used in patients with the following rare hereditary problems:
- Fructose intolerance
- Glucose-galactose malabsorption
- Sucrase-isomaltase insufficiency
4.2. Recommended Dose and Dosage Adjustment
Schizophrenia
Adults
Usual Dose: The recommended starting and target dose for aripiprazole is 10 or 15 mg/day (i.e., 10 to 15 mL/day) administered on a once-a-day schedule. Doses in the range of 10 to 30 mg/day have been established as effective in clinical trials. However, greater efficacy has not been demonstrated at doses higher than 10 mg/day. Dosage increases, if needed, should only be made after 2 weeks, the time needed to achieve steady state. The maximum daily dose should not exceed 30 mg/day (i.e., 30 mL/day).
Patients should be maintained on the lowest effective dose that provides optimal clinical response and tolerability and should be periodically reassessed to determine the need for maintenance treatment.
Adolescents (15-17 years of age)
Usual dose: The recommended target dose of aripiprazole is 10 mg/day administered on a once-a-day schedule. The recommended starting daily dose is 2 mg/day (i.e., 2 mL/day), titrated to 5 mg/day after 2 days and to the target dose of 10 mg/day after 2 additional days. Subsequent dose increases should be administered, if needed and as tolerated, in 5 mg/day (i.e., 5 mL/day) increments. Both the 10 mg/day and 30 mg/day doses have been shown to be effective in a double-blind, placebo-controlled clinical trial; however, the 30 mg/day dose was not shown to be more efficacious than the 10 mg/day dose.
The maximum daily dose should not exceed 30 mg/day. Patients should be maintained on the lowest effective dose that provides optimal clinical response and tolerability.
The safety and efficacy of aripiprazole during long term treatment have not been systematically evaluated in adolescent patients with schizophrenia. The physician who elects to use SOLUFY for extended periods in adolescent patients with schizophrenia should periodically re-evaluate the long-term usefulness of the drug for the individual patient.
Bipolar I Disorder
Adults
Monotherapy:
The recommended starting dose for aripiprazole as acute monotherapy is 15 mg given once a day.
Cotherapy with lithium or valproate:
The recommended starting dose for aripiprazole as acute and/or maintenance cotherapy with lithium or valproate at therapeutic serum levels is 10 to 15 mg given once daily.
The dose can be increased to 30 mg/day based on clinical response.
Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability. The maximum daily dose should not exceed 30 mg/day.
The physician who elects to use SOLUFY for extended periods in adult patients with bipolar I disorder should periodically re-evaluate the long-term usefulness of the drug for the individual patient.
Adolescents (13-17 years of age)
Monotherapy:
The recommended target dose is 10 mg/day, as acute monotherapy, administered on a once-a-day schedule. The recommended starting daily dose is 2 mg/day, titrated to 5 mg/day after 2 days and to the target dose of 10 mg/day after 2 additional days. Subsequent dose increases should be administered in 5 mg increments. The maximum daily dose should not exceed 30 mg/day.
The efficacy and safety of aripiprazole for the maintenance treatment of bipolar I disorder in the adolescent population have not been systematically evaluated.
Adjunctive Treatment of Major Depressive Disorder (MDD)
Adults
Usual dose: The recommended starting dose for aripiprazole as adjunctive treatment for patients already taking an antidepressant is 2 mg/day to 5 mg/day. The efficacy of aripiprazole as an adjunctive therapy for the treatment of major depressive disorder was established within a dose range of 2 mg/day to 15 mg/day. Dose adjustments of up to 5 mg/day should occur gradually, at intervals of no less than 1 week.
The short-term trials of adjunctive aripiprazole in MDD patients used a flexible dose regimen. Therefore, the minimum effective dose for this indication has not been established. Also, dose-relationship was not evaluated; however, some of the adverse events associated with aripiprazole showed dose-response in trials for other indications (see 7 Warnings and Precautions and 8.2 Clinical Trial Adverse Reactions). Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability.
The safety and efficacy of aripiprazole as an adjunct to antidepressant therapy have not been systematically evaluated in controlled trials beyond 6 weeks. Therefore, the required length of adjunctive treatment with SOLUFY is unknown. Thus, the physician who elects to use SOLUFY as an adjunct to an antidepressant in the treatment of MDD should use SOLUFY for the shortest period of time that is clinically indicated.
Pediatrics (< 18 years of age)
The safety and efficacy of aripiprazole for the treatment of MDD in patients under the age of 18 years have not been established and its use is not recommended.
Dosage adjustment
Concomitant use of strong CYP2D6 inhibitors, or strong CYP3A4 inhibitors or inducers:
- Strong CYP2D6 inhibitors: The aripiprazole dose should be reduced to one-half of its normal dose when co-administered with a strong CYP2D6 inhibitor (see 9.4 Drug-Drug Interactions). CYP2D6 metabolizing capacity should be considered when aripiprazole is co-administered with drugs that inhibit CYP2D6 (see 10.3 Pharmacokinetics, Special Populations and Conditions). When the strong CYP2D6 inhibitor is withdrawn from the combination therapy, the aripiprazole dose should be increased.
- Strong CYP3A4 inhibitors: The aripiprazole dose should be reduced to one-half of its normal dose when co-administered with a strong CYP3A4 inhibitor (see 9.4 Drug-Drug Interactions). When the strong CYP3A4 inhibitor is withdrawn from the combination therapy, the aripiprazole dose should be increased.
- Strong CYP3A4 inducers: The aripiprazole dose should be doubled when co-administered with a strong CYP3A4 inducer (see 9.4 Drug-Drug Interactions). Additional dose increases should be based on clinical evaluation. When the strong CYP3A4 inducer is withdrawn from the combination therapy, the aripiprazole dose should be reduced.
Special Populations
Geriatrics (≥ 65 years of age): Safety and efficacy of aripiprazole in patients 65 years of age or older have not been established. Given the greater sensitivity of this population, a lower starting dose may be considered when clinical factors warrant (see 7.1.4 Geriatrics).
SOLUFY is not indicated in geriatric patients with dementia (see 3 Serious Warnings and Precautions Box).
- Hepatic impairment: No dosage adjustment is required for patients with hepatic impairment.
- Renal impairment: No dosage adjustment is required for patients with renal impairment.
- Other special populations: No dosage adjustment is recommended based on gender, race, or smoking status (see 10.3 Pharmacokinetics, Special Populations and Conditions).
4.4. Administration
SOLUFY can be taken without regard to meals. A calibrated measuring cup and a 2 mL calibrated dropper are included in the carton.
Switching from Other Antipsychotics
There are no systematically collected data to specifically address switching patients with schizophrenia from other antipsychotics to SOLUFY or concerning concomitant administration with other antipsychotics. While immediate discontinuation of the previous antipsychotic treatment may be acceptable to some patients with schizophrenia, more gradual discontinuation may be most appropriate for others. In all cases, the period of overlapping antipsychotic administration should be minimized.
4.5. Missed Dose
If a patient misses a dose by a few hours, the patient should be advised to take their dose as soon as he/she remembers. If most of the day has passed, he/she should be advised to wait until the next scheduled dose. Patients should be advised to not take 2 doses of SOLUFY at once.
5. Overdose
Human Experience
In clinical studies, no deaths were associated with accidental or intentional acute overdosage of aripiprazole alone. In clinical trials, in the patient taking the largest confirmed amount of aripiprazole, 1080 mg, ingested with alcohol, the only symptom reported was vomiting.
In post-marketing experience, there is a single case of death that was possibly associated with accidental or intentional acute overdosage of aripiprazole alone. The patient ingested 900 mg of aripiprazole, was hospitalized in the intensive care unit for 10 to 14 days and died. The patient’s medical history included excessive alcohol use, although it is unclear whether alcohol was present at the time of overdosage. In the patient taking the largest confirmed amount of aripiprazole, 1680 mg, the only symptoms reported were vomiting, fatigue, and dizziness.
In addition, a report of non-fatal accidental overdose with aripiprazole alone (up to 195 mg) in a 2.5 years old child has been received. Vomiting, somnolence, lethargy, transient loss of consciousness and CNS depression were reported for this patient. Other potentially medically important signs and symptoms that have been observed during overdose included blood pressure increased and tachycardia. In the patients who were evaluated in hospital settings, there were no reported observations indicating clinically important adverse change in vital signs, laboratory assessments, or electrocardiogram.
Management of Overdosage
No specific information is available on the treatment of overdose with aripiprazole. Management of overdose should concentrate on supportive therapy, maintaining an adequate airway, oxygenation and ventilation, and management of symptoms. The possibility of multiple drug involvement should be considered. Therefore, cardiovascular monitoring should commence immediately and should include continuous electrocardiographic monitoring to detect possible arrhythmias. Following any confirmed or suspected overdose with aripiprazole, close medical supervision and monitoring should continue until the patient recovers.
Charcoal: In the event of an overdose of SOLUFY, an early charcoal administration may be useful in partially preventing the absorption of aripiprazole. Administration of 50 g of activated charcoal, one hour after a single 15 mg oral dose of aripiprazole, decreased the mean AUC and Cmax of aripiprazole by 50%.
Hemodialysis: Although there is no information on the effect of hemodialysis in treating an overdose with aripiprazole, hemodialysis is unlikely to be useful in overdose management since aripiprazole is highly bound to plasma proteins.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
SOLUFY is available in a 150 mL amber coloured bottle with a child-resistant screw cap.
7. Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing SOLUFY for patients who will be experiencing conditions which may contribute to an elevation in core body temperature, (e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration) (see 8 Adverse Reactions).
Carcinogenesis and Genotoxicity
For animal data, see 16 Non-Clinical Toxicology section.
Cardiovascular
Orthostatic Hypotension
Aripiprazole may be associated with orthostatic hypotension, perhaps due to its α1-adrenergic receptor antagonism. SOLUFY may induce orthostatic hypotension, tachycardia, dizziness, and sometimes syncope, especially at the initiation of treatment. The incidence of orthostatic hypotension-associated events from short-term, placebo-controlled trials of adult patients on oral aripiprazole (n=2643) included (aripiprazole incidence, placebo incidence): orthostatic hypotension (1.0%, 0.3%), postural dizziness (0.5%, 0.3%), and syncope (0.5%, 0.3%); of adolescent patients (13-17 years of age) with schizophrenia on oral aripiprazole (n=202) included (aripiprazole 10 mg/day incidence, aripiprazole 30 mg/day incidence, placebo incidence): orthostatic hypotension (0%, 2.9%, 0%), postural dizziness (0%, 2%, 0%), and syncope (1%, 0%, 0%); of pediatric and adolescent patients (10-17 years of age) with
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral | Solution, 1 mg/mL | Disodium edetate, fructose, glycerin, lactic acid, methylparaben, orange flavour, propylene glycol, propylparaben, purified water, sodium hydroxide, sucrose |
bipolar I disorder on oral aripiprazole (n=197) included (aripiprazole 10 mg/day incidence, aripiprazole 30 mg/day incidence, placebo incidence): orthostatic hypotension (1%, 0%, 0%), postural dizziness (0 %, 0%, 0%), and syncope (0%, 0%, 0%). The risk of orthostatic hypotension may be reduced by more gradual titration to the target dose.
The incidence of a significant orthostatic change in blood pressure (defined as a decrease in systolic blood pressure ≥20 mmHg accompanied by an increase in heart rate ≥25 bpm when comparing standing to supine values) for oral aripiprazole was (aripiprazole incidence, placebo incidence): 3.7%, 2.3% in adults; 0% (0/202), 0% (0/100) in adolescent patients (13-17 years of age) with schizophrenia and 0%, 1.1% in pediatric and adolescent patients (10-17 years of age) with bipolar I disorder, manic or mixed episode.
Aripiprazole should be used with caution in patients with known cardiovascular disease (e.g., history of myocardial infarction or ischemic heart disease, heart failure or conduction abnormalities), cerebrovascular disease, or conditions which would predispose patients to hypotension (e.g., dehydration, hypovolemia, and treatment with antihypertensive medications). Patients with a history of clinically significant cardiovascular disorders were excluded from clinical trials.
QT Interval
In clinical trials with aripiprazole involving patients with schizophrenia or bipolar mania, the incidence of QT prolongation was comparable to placebo. In post-marketing experience, QT prolongation has been reported very rarely with aripiprazole treatment. As with other antipsychotics, caution should be exercised when SOLUFY is prescribed in patients with a history of cardiac arrhythmias, in patients with congenital or family history of long QT syndrome, in patients with other conditions that predispose to arrhythmias (e.g., hypokalemia or hypomagnesemia or hypocalcemia), and in concomitant use with drugs known to prolong the QT interval ( see 8.2 Clinical Trial Adverse Reactions, ECG changes, 8.5 Post-Market Adverse Reactions and 9.4 Drug-Drug Interactions).
Dependence, Tolerance and/or Abuse Liability
Aripiprazole has not been systematically studied in humans for its potential for abuse, tolerance, or physical dependence. In physical dependence studies in monkeys, withdrawal symptoms were observed upon abrupt cessation of dosing. While the clinical trials did not reveal any tendency for any drug-seeking behavior, these observations were not systematic and it is not possible to predict on the basis of this limited experience the extent to which a CNS-active drug will be misused, diverted, or abused once marketed. Consequently, patients should be evaluated carefully for a history of drug abuse, and such patients should be observed closely for signs of SOLUFY misuse or abuse (e.g., development of tolerance, increases in dose, drug-seeking behavior).
Driving and Operating Machinery
Like other antipsychotics drugs, SOLUFY has the potential to impair judgment, thinking, or motor skills. Somnolence was a commonly reported adverse event in patients treated with aripiprazole in clinical trials. Somnolence (including sedation) adverse events were reported more frequently in adolescents with schizophrenia (13-17 years of age) or pediatric and adolescent patients with bipolar I disorder (10-17 years of age) than in adult patients (see 8.2 Clinical Trial Adverse Reactions, Somnolence).
Because SOLUFY may cause somnolence, and impair motor skills, patients should be cautioned not to drive, operate dangerous machinery or engage in activities that require alertness or physical coordination if they are experiencing any of these effects.
Endocrine and Metabolism
Hyperglycemia and Diabetes Mellitus
Diabetic ketoacidosis has occurred in patients with no reported history of hyperglycemia. As with some other antipsychotics, exacerbation of pre-existing diabetes and hyperglycemia have been reported rarely and diabetic ketoacidosis and diabetic coma including some fatal cases, have been reported very rarely during the use of aripiprazole (see 8.2 Clinical Trial Adverse Reactions, Other Adverse Events Observed During the Pre-Marketing Evaluation of Oral Aripiprazole).
Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies which did not include aripiprazole suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with the atypical antipsychotics. Because aripiprazole was not marketed at the time these studies were performed, it is not known if aripiprazole is associated with this increased risk. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available.
Patients should have baseline and periodic monitoring of blood glucose and body weight. Any patient treated with atypical antipsychotics should also be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Weight, Glucose and Lipid Changes in Adolescents with Schizophrenia or Pediatric and Adolescent Patients with Bipolar I Disorder
There are limited data for aripiprazole in adolescents with schizophrenia (13-17 years of age) or pediatric and adolescent patients with bipolar I disorder (10-17 years of age) from acute placebo controlled, fixed dose clinical trials 4 to 6 weeks, 10 mg/day and 30 mg/day) and from extension studies (up to 26 weeks of treatment) to assess the effects of aripiprazole on weight, glucose, and lipid metabolism. Data for these parameters from the acute placebo controlled clinical trials were from approximately 50 to 100 patients per treatment group, and in the adolescent schizophrenia trial the majority of patients had received treatment with other antipsychotic medications prior to inclusion in this study. Therefore, these data cannot be considered entirely predictive of the effects of aripiprazole on weight, glucose and lipid metabolism during use in adolescents with schizophrenia (see 8.2 Clinical Trial Adverse Reactions, Weight Gain and 8.2.1 Clinical Trial Adverse Reactions - Pediatrics). Published studies have demonstrated that the adverse effects of atypical antipsychotic drugs on weight, glucose and lipid metabolism can be greater in antipsychotic-naïve pediatric and adolescent patients than in patients who have been treated previously with antipsychotic drugs.
Clinical monitoring of weight, glucose and lipids at baseline and at regular intervals is recommended for adolescents with schizophrenia or bipolar I disorder who are treated with antipsychotics including SOLUFY.
Weight Gain
During acute placebo-controlled and extension phase studies in pediatric and adolescent patients with either schizophrenia or bipolar I disorder, the proportion of patients with potentially clinically significant weight gain (≥ 7% increase from baseline weight) was greater among those treated with aripiprazole compared to those that received placebo (see 8.2 Clinical Trial Adverse Reactions, Weight Gain).
Glucose
See 8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Lipids
See 8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Fructose or Sucrose Intolerance
SOLUFY contains fructose and sucrose (see 6 Dosage Forms, Strengths, Composition, and Packaging). Therefore, it should not be used in patients with the following rare hereditary problems:
- Fructose intolerance
- Glucose-galactose malabsorption
- Sucrase-isomaltase insufficiency
Genitourinary
Priapism
Rare cases of priapism have been reported with antipsychotic use such as aripiprazole. As with other psychotropic drugs, this adverse reaction did not appear to be dose-dependent and did not correlate with the duration of treatment.
Hematologic
In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including aripiprazole. Agranulocytosis has also been reported (see 8.2 Clinical Trial Adverse Reactions, Other Adverse Events Observed During the Pre-Marketing Evaluation of Oral Aripiprazole and 8.5 Post-Market Adverse Reactions). Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting SOLUFY and then periodically throughout treatment.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug-induced leukopenia/neutropenia. Patients with a history of a clinically significant low WBC or drug-induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and discontinuation of SOLUFY should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors.
Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Patients with severe neutropenia (absolute neutrophil count <1000/mm3) should discontinue SOLUFY and have their WBC followed until recovery.
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs, including aripiprazole in case reports and/or observational studies. When prescribing SOLUFY all potential risk factors for VTE should be identified and preventative measures undertaken.
Monitoring and Laboratory Tests
Monitoring for orthostatic vital signs is recommended in patients who may be vulnerable to hypotension (see 7 Warnings and Precautions, Cardiovascular).
Baseline measurement and periodic monitoring of blood glucose and body weight is recommended for all patients. In addition, baseline measurement and periodic monitoring of blood lipids is recommended for adolescents (see 7 Warnings and Precautions, Endocrine and Metabolism).
Frequent monitoring of CBC during the first few months of treatment is recommended in patients with a history of a clinically significant low WBC or drug-induced leukopenia/neutropenia. Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur (see 7 Warnings and Precautions, Hematologic).
Neurologic
Neuroleptic Malignant Syndrome (NMS)
Neuroleptic malignant syndrome is a potentially fatal symptom complex that has been reported in association with antipsychotic drugs, including aripiprazole.
Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.), and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
The management of NMS should include 1) immediate discontinuation of all antipsychotic drugs including SOLUFY and other drugs not essential to therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment for uncomplicated NMS.
If a patient requires antipsychotic drug treatment after recovery from NMS, the potential re-introduction of therapy should be very carefully considered. The patient should be carefully monitored, since recurrence of NMS has been reported.
Falls
Antipsychotics, including aripiprazole, may cause somnolence, postural hypotension, motor and sensory instability, which may lead to falls and, consequently, fractures or other injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, complete fall risk assessments when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Tardive Dyskinesia
A syndrome of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome is highest among geriatric patients, especially geriatric women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown.
The risk of developing tardive dyskinesia and the likelihood that it will become irreversible increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment, itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and, thereby, may possibly mask the underlying process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown.
Given these considerations, SOLUFY should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that (1) is known to respond to antipsychotic drugs and (2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of tardive dyskinesia appear in a patient on SOLUFY, drug discontinuation should be considered. However, some patients may require treatment with SOLUFY despite the presence of the syndrome.
In an open-label longer-term (up to 1 year) trial of aripiprazole adjunctive to antidepressants in patients with MDD, the incidence of tardive dyskinesia was 4/994 or 0.4%.
Extrapyramidal Symptoms
The rate of extrapyramidal-related adverse events in adolescents (13-17 years of age) with schizophrenia and in pediatric and adolescent (10-17 years) patients in a manic or mixed episode of bipolar I disorder was greater than the rate reported in adult patients (see 8.2 Clinical Trial Adverse Reactions, Dose-Related Adverse Events, Extrapyramidal Symptoms and 8.2 Clinical Trial Adverse Reactions, Additional Findings Observed in Clinical Trials).
Pediatric and adolescent patients are known to be at greater risk of experiencing certain adverse events related to the use of atypical antipsychotics, including extrapyramidal symptoms (see 8 Adverse Reactions).
Seizure / Convulsion
In short-term, placebo-controlled trials of patients treated with oral aripiprazole, seizures/convulsions occurred in 0.1% (3/2643) of adult patients; in 0% (0/202) of adolescent (13-17 years of age) patients with schizophrenia and in 0.5% (1/197) of pediatric and adolescent patients with bipolar I disorder (10-17 years of age). There were confounding factors that may have contributed to the occurrence of seizures in some of these patients.
As with other antipsychotic drugs, aripiprazole should be used cautiously in patients with a history of seizures or with conditions that lower the seizure threshold. Conditions that lower the seizure threshold may be more prevalent in a population of 65 years or older.
Psychiatric
Suicide
The possibility of a suicide attempt is inherent in psychotic illnesses, bipolar disorder and major depressive disorder (MDD). Also, in addition to depressive episodes associated with bipolar disorder and MDD, depression may be co-morbid with schizophrenia. The risk of suicide-related events during a depressive episode may persist until remission occurs. It is general clinical experience that the risk of suicide may increase in the early stages of recovery. Close supervision and appropriate clinical management of high-risk patients should accompany drug therapy. Prescription of SOLUFY should be written for the smallest quantity consistent with good patient management, in order to reduce the risk of overdose.
Pathological Gambling and Other Impulse-Control Disorders
Post-marketing reports of pathological gambling have been reported in patients treated with aripiprazole. These reports suggest that patients can experience increased urges, particularly for gambling, and the inability to control these urges while taking aripiprazole. With regards to pathological gambling, patients with a prior history of gambling disorder may be at increased risk and should be monitored carefully. Other urges, reported very rarely, include: increased sexual urges, compulsive spending, binge or compulsive eating, and other impulsive and compulsive behaviors. Because patients may not recognize these behaviors as abnormal, it is important for prescribers to ask patients or their caregivers specifically about the development of new or increased gambling urges, sexual urges, compulsive spending, binge or compulsive eating, or other urges while being treated with aripiprazole. It should be noted that impulse- control symptoms can be associated with the underlying disorder; however, in some cases, although not all, urges were reported to have stopped when the dose was reduced or the medication was discontinued. Although impulse-control disorders have been reported very rarely, impulse-control disorders may result in harm to the patient and others if not recognized. Consider dose reduction or stopping the medication if a patient develops such urges while taking aripiprazole.
Skin
Severe Cutaneous Adverse Reactions (SCARs)
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP) are potentially life- threatening adverse drug reactions that have been reported with atypical antipsychotic exposure (see 8.5 Post-Market Adverse Reactions). SCARs commonly present as a combination of the following symptoms: extensive cutaneous rash or exfoliative dermatitis, fever, lymphadenopathy and possible eosinophilia. Discontinue SOLUFY if severe cutaneous adverse reactions occur.
7.1. Special Populations
7.1.1. Pregnancy
Teratogenic Effects
There are no adequate and well-controlled studies in pregnant women. It is not known whether aripiprazole can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity. In animal studies, aripiprazole demonstrated developmental toxicity, including possible teratogenic effects in rats and rabbits (see 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology).
Non-Teratogenic Effects
Neonates exposed to antipsychotic drugs, including SOLUFY, during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
SOLUFY should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus.
Labor and Delivery
The effect of aripiprazole on labor and delivery in humans is unknown.
7.1.2. Breastfeeding
Aripiprazole is excreted in human breast milk. It is recommended that women receiving aripiprazole should not breastfeed.
See also 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology.
7.1.3. Pediatrics
Pediatrics (< 18 years of age): When prescribing to adolescents with schizophrenia (15-17 years of age) or adolescents in a manic or mixed episode of bipolar I disorder (13-17 years of age), clinicians must take into account the safety concerns associated with all antipsychotic drugs which include: weight gain; hyperlipidemia; hyperglycemia; and, extrapyramidal effects which can be more frequent or more severe in this patient population than in adults (see 7 Warnings and Precautions, Endocrine and Metabolism, 7 Warnings and Precautions, Neurologic, 8.2 Clinical Trial Adverse Reactions and 8.2.1 Clinical Trial Adverse Reactions - Pediatrics). SOLUFY should only be prescribed to adolescents with schizophrenia or bipolar I disorder by clinicians who are experienced in the diagnosis and treatment of adolescents with psychiatric illness and who are experienced in the early detection and management of the above-mentioned safety issues associated with this class of drugs.
Weight gain has been observed with atypical antipsychotic use in pediatric and adolescent patient populations. Independent of any drug-specific effects, weight gain can be associated with adverse changes in other metabolic parameters (e.g., glucose and lipid metabolism). Abnormal childhood weight and metabolic status can have adverse effects on cardiovascular outcomes in adulthood. Weight gain and adverse effects on other metabolic parameters associated with atypical antipsychotics can be more frequent or severe in pediatric and adolescent patients than in the adult patients.
The long-term safety, including cardiometabolic effects and effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
SOLUFY is not indicated for the treatment of schizophrenia in adolescents under 15 years of age due to insufficient safety and efficacy data (see 8 Adverse Reactions and 14.1 Clinicals Trials by Indication, Schizophrenia, Adolescents).
SOLUFY is not indicated for treatment of manic or mixed episodes of bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data (see 8 Adverse Reactions and 14.1 Clinical Trials by Indication, Bipolar I Disorder, Pediatric and Adolescent).
The safety and efficacy of aripiprazole in patients with major depressive disorder (MDD) under the age of 18 years have not been established and its use is not recommended.
7.1.4. Geriatrics
The safety and efficacy of aripiprazole in patients 65 years of age or older have not been established. Caution should be used when treating geriatric patients.
Placebo-controlled studies of oral aripiprazole in schizophrenia, bipolar mania or major depressive disorder did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
In formal single-dose pharmacokinetic studies (with aripiprazole given in a single dose of 15 mg), aripiprazole clearance was 20% lower in geriatric (≥65 years) subjects compared to younger adult subjects (18 to 64 years). There was no detectable age effect, however, in the population pharmacokinetic analysis in schizophrenia patients. Also, the pharmacokinetics of aripiprazole after multiple doses in geriatric patients appeared similar to that observed in young, healthy subjects (see 3 Serious Warnings and Precautions Box and 4.2 Recommended Dose and Dosage Adjustment).
Nevertheless, geriatric patients generally have decreased cardiac, hepatic and renal function, and more frequent use of concomitant medication. The presence of multiple factors that might increase the pharmacodynamic response to aripiprazole, or cause poorer tolerance or orthostasis, should lead to consideration of a lower starting dose, slower titration, and careful monitoring during the initial dosing period for geriatric patients.
Use in Geriatric Patients with Dementia
Overall Mortality
Geriatric patients with dementia treated with oral atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of 13 placebo-controlled trials of various atypical antipsychotic drugs (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. In three placebo-controlled studies of aripiprazole in geriatric patients with Alzheimer’s disease (n=938; mean age: 82.4 years; range: 56-99 years), the rate of death in aripiprazole-treated patients was 3.5%, compared to a rate of 1.7% in the placebo group during or within 30 days after termination from the double-blind phase of the studies. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature.
SOLUFY is not indicated for the treatment of geriatric patients with dementia (see 3 Serious Warnings and Precautions Box).
Cerebrovascular Adverse Events, Including Stroke in Geriatric Patients with Dementia
In placebo-controlled clinical studies (two flexible dose and one fixed dose study) of geriatric patients with dementia, there was an increased incidence of cerebrovascular adverse events (e.g., stroke, transient ischemic attack), including fatalities, in aripiprazole-treated patients. In the fixed-dose study, there was a statistically significant dose response relationship for cerebrovascular adverse events in patients treated with aripiprazole. Aripiprazole is not indicated for the treatment of geriatric patients with dementia (see 3 Serious Warnings and Precautions Box).
Frequent Treatment Emergent Adverse Events in Geriatric Patients with Dementia
In the placebo-controlled studies of geriatric patients with dementia (n=595 treated with aripiprazole, n=343 treated with placebo), the following treatment-emergent adverse events were reported at an incidence of ≥3% and aripiprazole incidence at least twice that for placebo: lethargy [placebo 2%, aripiprazole 5%], somnolence (including sedation) [placebo 3%, aripiprazole 8%], and incontinence (primarily, urinary incontinence) [placebo 1%, aripiprazole 5%], excessive salivation (placebo 0%, aripiprazole 4%), and lightheadedness (placebo 1%, aripiprazole 4%).
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use, including aripiprazole. Aspiration pneumonia is a common cause of morbidity and mortality in geriatric patients, particularly in those with advanced Alzheimer’s dementia. Aripiprazole and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia (see 8 Adverse Reactions).
The emergence of difficulty swallowing or excessive somnolence, could predispose patients to accidental injury or aspiration (see 3 Serious Warnings and Precautions Box).
8. Adverse Reactions
8.1. Adverse Reaction Overview
Aripiprazole was evaluated for safety in 13,543 adult patients who participated in multiple-dose, clinical trials in schizophrenia, bipolar disorder, major depressive disorder, dementia of the Alzheimer's type, Parkinson’s disease, and alcoholism, and who had approximately 7619 patient-years of exposure to oral aripiprazole and 749 patients with exposure to aripiprazole injection. A total of 3390 patients were treated with oral aripiprazole for at least 180 days and 1933 patients treated with oral aripiprazole had at least 1 year of exposure.
The conditions and duration of treatment with aripiprazole (monotherapy or adjunctive therapy with antidepressants or mood stabilizers) included (in overlapping categories) double-blind, comparative and noncomparative open-label studies, inpatient and outpatient studies, fixed- and flexible-dose studies, and short- and longer-term exposure.
Aripiprazole was evaluated for safety in 202 adolescent patients (13-17 years of age) with schizophrenia in a 6-week placebo-controlled clinical trial. Adolescent patients from this study were also treated with oral aripiprazole in uncontrolled, open-label studies for more than 26 weeks (n=178) and more than 52 weeks (n=79). Treatment-emergent adverse event frequencies are reported for adolescent patients, 13-17 years of age, with schizophrenia that were included in these studies, but the majority of patients were 15-17 years of age.
Aripiprazole was evaluated for safety in 233 pediatric and adolescent patients (10-17 years) who participated in multiple-dose, clinical trials in bipolar I disorder. A total of 103 pediatric and adolescent patients with bipolar I disorder were treated with oral aripiprazole for more than 26 weeks. Treatment-emergent adverse frequencies are reported for pediatric and adolescent patients, 10-17 years of age in a manic or mixed episode of bipolar I disorder, but the majority of patients were 13-17 years of age.
SOLUFY is not indicated for the treatment of schizophrenia in adolescent patients under 15 years or for the treatment of manic or mixed episodes of bipolar I disorder in patients under 13 years of age due to insufficient safety and efficacy data (see 8 Adverse Reactions, 14.1 Clinical Trials by Indication, Schizophrenia, Adolescents and 14.1 Clinical Trials by Indication, Bipolar I Disorder, Pediatric and Adolescent).
Adverse events during exposure were obtained by collecting volunteered adverse events, as well as results of physical examinations, vital signs, weights, laboratory analyses, and ECG. Adverse events were recorded by clinical investigators using terminology of their own choosing. In the tables and tabulations that follow, MedDRA dictionary terminology has been used to classify reported adverse events into a smaller number of standardized event categories, in order to provide a meaningful estimate of the proportion of individuals reporting adverse events.
The stated frequencies of adverse events represent the proportion of individuals who reported at least once, a treatment-emergent adverse event of the type listed. An event was considered treatment emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation. There was no attempt to use investigator causality assessments; i.e. all events meeting the defined criteria, regardless of investigator causality are included.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Short-Term, Placebo-Controlled Trials of Adult Patients with Schizophrenia
The following findings are based on a pool of five placebo-controlled trials (four 4-week and one 6-week) in which aripiprazole was administered orally in doses ranging from 2 to 30 mg/day.
Adverse Events Associated with Discontinuation of Treatment
Overall, there was little difference in the incidence of discontinuation due to adverse events between aripiprazole-treated (7%) and placebo-treated (9%) patients. The types of adverse events that led to discontinuation were similar between the aripiprazole and placebo-treated patients.
Commonly Reported Adverse Events
The only commonly observed adverse event associated with the use of aripiprazole in patients with schizophrenia (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) was akathisia (placebo 4%; aripiprazole 8%).
Short-Term, Placebo-Controlled Trials of Aripiprazole in Adult Patients with Bipolar Mania
The following findings are based on a pool of 3-week, placebo-controlled, bipolar mania trials in which aripiprazole was administered orally at doses of 15 or 30 mg/day.
Adverse Events Associated with Discontinuation of Treatment
Overall, in patients with bipolar mania, there was little difference in the incidence of discontinuation due to adverse events between aripiprazole-treated (11%) and placebo-treated (10%) patients. The types of adverse events that led to discontinuation were similar between the aripiprazole and placebo-treated patients. Akathisia, the most common adverse event leading to discontinuation in the aripiprazole group, led to withdrawal of 2% of aripiprazole-treated patients and 0.3% of patients on placebo.
Commonly Reported Adverse Events
Commonly reported adverse events associated with the use of aripiprazole in patients with bipolar mania (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) are shown in Table 2.
Table 2: Commonly Reported Adverse Events in Short-Term, Placebo-Controlled Trials of Adult Patients with Bipolar Mania Treated with Aripiprazole
Percentage of Patients Reporting Event
Aripiprazole
Placebo
Preferred Term
(n=917)
(n=753)
Akathisia
13
4
Sedation
8
3
Restlessness
6
2
Extrapyramidal Disorder
5
2
Adverse Events Reported at an Incidence of 2% or More Among Adult Aripiprazole-Treated Patients and Greater than Placebo in Short-Term, Schizophrenia and Bipolar Mania Placebo-Controlled Trials
Table 3 enumerates the pooled incidence, rounded to the nearest percent, of treatment-emergent adverse events that were reported during acute therapy (up to 6 weeks in schizophrenia and up to 3 weeks in bipolar mania), including only those events that were reported in 2% or more of patients treated with aripiprazole (doses ≥2 mg/day) and for which the incidence in patients treated with aripiprazole was greater than the incidence in patients treated with placebo in the combined dataset.
Table 3: Treatment-Emergent Adverse Events in Short-Term, Placebo-Controlled Trials in Adult Patients with Schizophreniaa or Bipolar Maniab Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventc
System Organ Class
Aripiprazole
Placebo
Preferred Term
(n=1843)
(n=1166)
Eye Disorders
Blurred Vision
3
1
Gastrointestinal Disorders
Nausea
15
11
Constipation
11
7
Vomiting
11
6
Dyspepsia
9
7
Dry Mouth
5
4
Toothache
4
3
Abdominal Discomfort
3
2
Stomach Discomfort
3
2
General Disorders and Administration Site Conditions
Fatigue
6
4
Pain
3
2
Musculoskeletal and Connective Tissue Disorders
Musculoskeletal Stiffness
4
3
Pain in Extremity
4
2
Myalgia
2
1
Muscle Spasms
2
1
Nervous System Disorders
Headache
27
23
Dizziness
10
7
Akathisia
10
4
Sedation
7
4
Extrapyramidal Disorder
5
3
Tremor
5
3
Somnolence
5
3
Psychiatric Disorders
Agitation
19
17
Insomnia
18
13
Anxiety
17
13
Restlessness
5
3
Respiratory, Thoracic, and Mediastinal Disorders
Pharyngolaryngeal Pain
3
2
Cough
3
2 a 926 aripiprazole-treated patients and 413 placebo treated patients
b 917 aripiprazole-treated patients and 753 placebo-treated patients
c Events reported by at least 2% of patients treated with oral aripiprazole, except events which had an incidence equal to or less than placebo.
An examination of population subgroups did not demonstrate a difference in the incidence of adverse events based on age, gender, or race.
Patients should be advised of the risk of severe constipation during SOLUFY treatment and that they should tell their doctor if constipation occurs or worsens as they may need laxatives.
Short-Term, Placebo-Controlled Trial of Adjunctive Therapy in Adult Patients with Bipolar Mania
In a placebo-controlled trial of patients with bipolar mania who were already tolerating either lithium or valproate as monotherapy, aripiprazole was administered orally for 6 weeks at doses of 15 or 30 mg/day as adjunctive therapy with lithium or valproate. The adverse events reported in that study were generally similar to the adverse events listed in Table 2 from clinical trials in which aripiprazole was used as monotherapy. Akathisia and tremor were reported more frequently when aripiprazole was used as adjunctive therapy. Akathisia was reported in 19% of patients treated with aripiprazole as adjunctive therapy compared to 5% of patients who received placebo as adjunctive therapy. In the lithium subgroup, the incidence of akathisia was 28% in patients treated with aripiprazole as adjunct and 4% in patients treated with placebo. In the valproate subgroup akathisia was reported in 12% of patients treated with aripiprazole as adjunctive therapy compared to 6% treated with placebo as adjunctive therapy. The incidence of tremor was 9% for patients treated with aripiprazole as adjunctive therapy and 6% for patients who received placebo as adjunctive therapy. Other commonly reported adverse events in this trial were insomnia 8% vs 4% and extrapyramidal disorder 5% vs 1%, in aripiprazole-treated patients and placebo-treated patients, respectively.
Discontinuation rates due to adverse events were 12% for patients treated with adjunctive aripiprazole compared to 6% for patients treated with adjunctive placebo. Akathisia, the most common adverse event leading to discontinuation in the aripiprazole group, led to withdrawal of 5% of aripiprazole-treated patients and 1% of patients on placebo.
Short-Term, Placebo-Controlled Trial of Adolescent Patients (13-17 years of age) with Schizophrenia
The following findings are based on one 6-week placebo-controlled trial in which oral aripiprazole was administered in doses ranging from 2 mg/day to 30 mg/day. Doses were titrated to fixed doses of 10 mg/day or 30 mg/day aripiprazole.
Adverse Events Associated with Discontinuation of Treatment
The incidence of discontinuation due to adverse events was 7% for patients treated with 10 mg/day aripiprazole, 3.9% for patients treated with 30 mg/day aripiprazole and 2% for patients treated with placebo.
Commonly Observed Adverse Events
Commonly observed adverse events associated with the use of aripiprazole in adolescent patients with schizophrenia (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) were extrapyramidal disorder, somnolence, and tremor.
Adverse Events Reported at an Incidence of 1% or More Among Aripiprazole-Treated Patients and Greater than Placebo in a Short-Term, Schizophrenia Placebo-Controlled Trial in Adolescents (13-17 years of age)
Table 4 enumerates the incidence, rounded to the nearest percent, of treatment-emergent adverse events that were reported during acute therapy (up to 6 weeks in schizophrenia) with 10 mg/day and 30 mg/day aripiprazole compared to placebo. Only adverse events that were reported in 1% or more of adolescent patients treated with aripiprazole (doses ≥2 mg/day) and for which the incidence in patients treated with aripiprazole was greater than the incidence in patients treated with placebo are included in Table 4.
Table 4: Treatment-Emergent Adverse Events in a 6-week, Placebo-Controlled Trial in Adolescent Patientsa with Schizophrenia Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventb
System Organ Class
Aripiprazole
10 mg
Aripiprazole
30 mg
Placebo
Preferred Term
(n=100)
(n=102)
(n=100)
Cardiac Disorders
Tachycardia
2
0
0
Sinus bradycardia
1
1
0
Eye Disorders
Vision blurred
2
0
0
Gastrointestinal Disorders
Nausea
9
10
Constipation
3
2
1
Diarrhea
2
3
0
Dry Mouth
1
3
1
Salivary Hypersecretion
1
3
1
Stomach discomfort
1
1
0
General Disorders and Administration Site Conditions
Fatigue
4
3
1
Pain
1
1
0
Infections and Infestations
Nasopharyngitis
5
5
4
Upper Respiratory Tract Infection
1
2
0
Influenza
1
1
0
Viral Infection
1
1
0
Investigations
Blood Glucose Increased
3
0
0
Blood insulin increased
2
0
0
Weight Increased
1
2
0
Metabolism and Nutrition Disorders
Increased Appetite
4
2
0
Musculoskeletal and Connective Tissue Disorders
Arthralgia
1
1
0
Table 4: Treatment-Emergent Adverse Events in a 6-week, Placebo-Controlled Trial in Adolescent Patientsa with Schizophrenia Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventb
System Organ Class
Aripiprazole
10 mg
Aripiprazole
30 mg
Placebo
Preferred Term
(n=100)
(n=102)
(n=100)
Muscle rigidity
1
1
0
Muscle weakness
1
1
0
Pain in Extremity
0
3
1
Nervous System Disorders
Extrapyramidal Disorder
13
22
5
Somnolencec
11
22
6
Headache
16
11
10
Akathisia
5
12
5
Tremor
2
12
2
Dizziness
7
4
3
Dystonia
3
1
0
Dizziness postural
0
2
0
Drooling
0
3
0
Dysarthria
2
0
0
Dyskinesia
1
2
0
Psychiatric Disorders
Hallucination, auditory
2
0
0
Respiratory, Thoracic and Mediastinal Disorders
Hiccups
0
2
0
Skin and Subcutaneous Tissue Disorders
Rash
3
1
0
Ecchymosis
1
1
0
Vascular Disorders
Orthostatic Hypotension
0
3
0
- a Treatment-emergent adverse event incidences are based on the safety population that included patients 13-17 years of age, but 75% patients were 15-17 years of age. Aripiprazole is not indicated for patients with schizophrenia < 15 years of age due to insufficient safety and efficacy data.
- b Events reported by at least 1% of 202 adolescent patients treated with oral aripiprazole, except events which had an incidence equal to or less than placebo.
- c Incidence of somnolence does not include sedation. Sedation was reported in one patient receiving 10 mg/day aripiprazole.
Short-Term (4-week), Placebo-Controlled Trial of Pediatric and Adolescent Patients (10-17 years of age) with a Manic or Mixed Episode of Bipolar I Disorder
The following findings are based on one 4-week placebo-controlled trial in which oral aripiprazole was administered in doses of 10 mg/day or 30 mg/day.
Adverse Events Associated with Discontinuation of Treatment
The incidence of discontinuation due to adverse events between aripiprazole-treated and placebo-treated pediatric and adolescent patients (10-17 years) was 6% (10 mg/day), 8% (30 mg/day) and 2%, respectively.
Commonly Observed Adverse Events
Commonly observed adverse events associated with the use of aripiprazole in pediatric and adolescent patients with bipolar I disorder (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) were somnolence, extrapyramidal disorder, fatigue, nausea, akathisia, blurred vision, salivary hypersecretion, and dizziness.
Adverse Events Reported at an Incidence of 1% or More Among Aripiprazole-Treated Patients and Greater than Placebo in a Short-Term, Bipolar I Disorder Placebo-Controlled Trial in Pediatric and Adolescent Patients (10-17 years of age).
Table 5 enumerates the pooled incidence, rounded to the nearest percent, of treatment- emergent adverse events that were reported during acute therapy (up to 4 weeks in bipolar I disorder), including only those events that were reported in 1% or more of pediatric and adolescent patients (10-17 years of age) treated with aripiprazole (doses ≥2 mg/day) and for which the incidence in patients treated with aripiprazole was greater than the incidence in patients treated with placebo.
Table 5: Treatment-Emergent Adverse Events in a Short-Term, Placebo-Controlled Trial in Pediatric and Adolescenta Patients (10-17 yrs) with Bipolar I Disorder Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventb
System Organ Class
Aripiprazole 10 mg
Aripiprazole 30 mg
Placebo
Preferred Term
(n=98)
(n=99)
(n=97)
Blood and Lymphatic System Disorders
Anemia
1
1
0
Eye Disorders
Vision blurred
8
8
0
Gastrointestinal Disorders
Nausea
9
12
4
Diarrhea
4
4
0
Dry Mouth
1
1
0
Salivary Hypersecretion
3
8
0
Abdominal Pain Upper
4
5
3
Abdominal Pain
1
1
0
Stomach discomfort
2
4
2
General Disorders and Administration Site Conditions
Fatigue
13
9
4
Irritability
1
1
0
Pyrexia
3
4
0
Asthenia
0
2
0
Table 5: Treatment-Emergent Adverse Events in a Short-Term, Placebo-Controlled Trial in Pediatric and Adolescenta Patients (10-17 yrs) with Bipolar I Disorder Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventb
System Organ Class
Aripiprazole 10 mg
Aripiprazole 30 mg
Placebo
Preferred Term
(n=98)
(n=99)
(n=97)
Infections and Infestations
Nasopharyngitis
4
3
1
Pharyngitis Streptococcal
2
0
0
Gastroenteritis Viral
1
3
1
Injury, Poisoning and Procedural Complications
Joint Sprain
2
1
0
Muscle Strain
2
0
0
Self Mutilation
1
1
0
Investigations
Weight Increased
4
3
1
Blood Creatinine Phosphokinase Increased
1
3
0
Heart Rate Increased
0
2
0
Metabolism and Nutrition Disorders
Decreased Appetite
6
3
3
Increased Appetite
2
5
3
Musculoskeletal and Connective Tissue Disorders
Back Pain
2
2
1
Neck Pain
2
0
0
Muscle Twitching
1
1
0
Arthralgia
1
3
0
Pain in Extremity
1
1
0
Nervous System Disorders
Somnolence
19
26
3
Headache
17
19
17
Extrapyramidal Disorder
12
27
3
Akathisia
8
11
2
Dizziness
5
5
1
Sedation
2
2
0
Dyskinesia
2
0
0
Tremor
1
3
1
Lethargy
1
2
0
Dystonia
0
5
0
Hypersomnia
0
2
0
Disturbance in Attention
0
2
0
Psychiatric Disorders
Insomnia
4
1
1
Aggression
2
0
0
Oppositional Defiant Disorder
2
0
0
Table 5: Treatment-Emergent Adverse Events in a Short-Term, Placebo-Controlled Trial in Pediatric and Adolescenta Patients (10-17 yrs) with Bipolar I Disorder Treated with Oral Aripiprazole
Percentage of Patients Reporting Eventb
System Organ Class
Aripiprazole 10 mg
Aripiprazole 30 mg
Placebo
Preferred Term
(n=98)
(n=99)
(n=97)
Restlessness
2
1
0
Suicidal Ideation
1
1
0
Reproductive System and Breast Disorders
Dysmenorrhea
2
0
0
Respiratory, Thoracic and Mediastinal Disorders
Epistaxis
1
2
1
Tonsillar Hypertrophy
1
1
0
Skin and Subcutaneous Tissue Disorders
Rash
1
2
1
Acne
0
2
0 a Treatment-emergent adverse event incidences are based on the safety population that included patients 10-17 years of age, but 63% patients were 13-17 years of age. Aripiprazole is not indicated for patients with bipolar I disorder < 13 years of age due to insufficient safety and efficacy data.
b Events reported by at least 1% of 197 pediatric and adolescent patients treated with oral aripiprazole, except events which had an incidence equal to or less than placebo.
Short-Term Placebo-Controlled Trials in Patients Receiving Aripiprazole as Adjunctive Treatment for Major Depressive Disorder (MDD)
The following findings are based on a pool of three placebo-controlled trials of adjunctive aripiprazole in patients with MDD who had an inadequate response to at least two treatments with antidepressants in the current episode, one of them demonstrated prospectively, in which aripiprazole was administered at doses of 2 mg to 20 mg as adjunctive treatment to continued antidepressant therapy for up to 6 weeks.
Adverse Events Associated with Discontinuation of Treatment
The incidence of discontinuation due to adverse events was 6% for adjunctive aripiprazole-treated patients and 2% for adjunctive placebo-treated patients. Akathisia, the most common adverse event leading to discontinuation in the aripiprazole group, led to withdrawal of 1.3% of aripiprazole-treated patients and 0% of patients on placebo.
Commonly Reported Adverse Events
Commonly reported adverse events associated with the use of adjunctive aripiprazole in patients with MDD (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) were: akathisia, restlessness, fatigue, insomnia, blurred vision, somnolence, and constipation.
Adverse Events Reported at an Incidence of 2% or More in Adult Patients with Major Depressive Disorder
Table 6 enumerates the pooled incidence, rounded to the nearest percent, of treatment-emergent adverse events that were reported during acute therapy (up to 6 weeks), including only those adverse events that occurred in 2% or more of patients treated with adjunctive aripiprazole (doses ≥2 mg/day)
and for which the incidence in patients treated with adjunctive aripiprazole was greater than the incidence in patients treated with adjunctive placebo in the combined dataset.
Table 6: Treatment Emergent Adverse Events in Short-Term, Placebo-Controlled Adjunctive Trials of Adult Patients with Major Depressive Disorder (flexible doses of 2 to 20 mg/day)
Percentage of Patients Reporting Eventa
System Organ Class
Aripiprazole+ADT*
Placebo+ADT*
Preferred Term
(n=547)
(n=538)
Eye Disorders
Blurred Vision
6
2
Gastrointestinal Disorders
Constipation
5
2
Dyspepsia
2
1
General Disorders and Administration Site Conditions
Fatigue
9
4
Feeling Jittery
2
1
Irritability
2
1
Infections and Infestations
Upper Respiratory Tract Infection
6
5
Nasopharyngitis
3
2
Investigations
Weight Increased
3
2
Metabolism and Nutrition Disorders
Increased Appetite
3
2
Musculoskeletal and Connective Tissue Disorders
Arthralgia
4
2
Myalgia
3
1
Nervous System Disorders
Akathisia
23
4
Somnolence
6
3
Dizziness
4
2
Sedation
4
2
Disturbance in Attention
2
1
Psychiatric Disorders
Restlessness
12
2
Insomnia
8
3 a Adverse events reported by at least 2% of patients treated with adjunctive aripiprazole, except adverse reactions which had an incidence equal to or less than placebo.
* Antidepressant Therapy
Dose-Related Adverse Events
Schizophrenia
Dose response relationships for the incidence of treatment-emergent adverse events were evaluated from four trials in adult patients with schizophrenia comparing various fixed oral doses (2, 5, 10, 15, 20, or 30 mg/day) of aripiprazole to placebo. This analysis, stratified by study, indicated that the only adverse event to have a possible dose response relationship, and then most prominent only with 30 mg/day, was somnolence [including sedation]; (incidences were placebo, 7.4%; 10 mg/day, 8.5%; 15 mg/day, 8.7%; 20 mg/day, 7.5%; 30 mg/day, 12.6%).
In the study of adolescent patients with schizophrenia, four adverse events appeared to have a possible dose response relationship: extrapyramidal disorder (incidences were placebo, 5.0%; 10 mg/day, 13.0%; 30 mg/day, 21.6%); somnolence (incidences were placebo, 6.0%; 10 mg/day, 11.0%; 30 mg/day, 21.6%); akathisia (incidences were placebo, 5.0%; 10 mg/day, 5.0%; 30 mg/day, 11.8%); and tremor (incidences were placebo, 2.0%; 10 mg/day, 2.0%; 30 mg/day, 11.8%). Orthostatic hypotension adverse events also appeared to have a possible dose response relationship (see 7 Warnings and Precautions, Cardiovascular).
Bipolar I Disorder
In two clinical trials in adult patients with bipolar mania comparing flexible doses of 15 or 30 mg/day of oral aripiprazole to placebo, no dose response relationship for treatment-emergent adverse events was found. In the study of pediatric and adolescent patients (10-17 years of age) with bipolar I disorder, four common adverse events had a possible dose response relationship at 4 weeks : extrapyramidal disorder (incidences were placebo, 3.1%; 10 mg/day, 12.2%; 30 mg/day, 27.3%); somnolence (incidences were placebo, 3.1%; 10 mg/day, 19.4%; 30 mg/day, 26.3%); akathisia (incidences were placebo, 2.1%; 10 mg/day, 8.2%; 30 mg/day, 11.1%); and salivary hypersecretion (incidences were placebo, 0%; 10 mg/day, 3.1%; 30 mg/day, 8.1%).
Major Depressive Disorder (MDD)
The safety of aripiprazole as adjunct treatment in patients with MDD who had inadequate response to prior antidepressant treatment was evaluated in 3 short-term (6-weeks) trials. Those trials used a flexible-dose regimen, with an aripiprazole starting dose of 5 mg/day, and allowable doses in the 2-20 mg/day range afterwards. Therefore, in these trials dose-response was not evaluated.
Extrapyramidal Symptoms
Table 7 and Table 8 provide the percentage of patients reporting treatment-emergent extrapyramidal symptoms in short-term placebo-controlled trials in adults and pediatrics, respectively.
Table 7: Percentage of Adult Patients Reporting Treatment-Emergent Extrapyramidal Symptoms in Short-Term Placebo-Controlled Trials
Percentage of Patients Reporting Event
Schizophrenia (dose range 2-30 mg/day)
Bipolar Mania Monotherapy (dose range 15-30 mg/day)
Bipolar Mania Cotherapy
(dose range 15-30 mg/day)
Adjunctive in MDD (dose range 2-20 mg/day)
Aripi- prazole
Placebo
Aripi- prazole
Placebo
Aripi prazole
Placebo
Aripi- prazole
Placebo
EPS-
related AEsa (excluding akathisia)
14
14
16
8
15
8
8
5
Akathisia- related
events
8
4
13
4
19
5
23
4 a EPS-related AEs included Parkinsonism events, dystonic events, dyskinetic events and residual events such as muscle twitching and myoclonus.
The incidence of reported EPS-related events in the placebo controlled trial in adolescent patients with schizophrenia and in pediatric and adolescent patients with bipolar I disorder was greater than the incidence reported for adult schizophrenia and bipolar patients (Table 7 and Table 8).
Table 8: Percentage of Children and Adolescent Patients Reporting Treatment-Emergent Extrapyramidal Symptoms in Short-Term Placebo-Controlled Trials
Percentage of Patients Reporting Event
Schizophrenia a
Bipolar I Disorder b
Aripiprazole
Aripiprazole
10 mg
30 mg
Placebo
10 mg
30 mg
Placebo
EPS-related AEsc (excluding
akathisia)
18
32
7
17
34
5
Akathisia-related events
6
12
6
8
12
2
- a Six-week schizophrenia trial of adolescent patients age 13-17
- b Four-week bipolar I disorder trial of pediatric and adolescent patients age 10-17
- c EPS-related AEs included Parkinsonism events, dystonic events, dyskinetic events and residual events such as muscle twitching and myoclonus.
Commonly reported treatment-emergent extrapyramidal symptoms in adolescent schizophrenia patients and pediatric and adolescent patients with bipolar I disorder were generally dose-related.
Table 9 and Table 10 provide the mean change from baseline to endpoint score on the Simpson Angus Rating Scale (for EPS) (SAS), Barnes Akathisia Scale (for akathisia), and the Assessments of Involuntary Movement Scales (for dyskinesia) (AIMS) from short-term, placebo-controlled trials in adults and pediatrics, respectively.
Table 9: Mean change from baseline to endpoint score on the SAS, Barnes Akathisia Scale, and AIMS from short-term placebo-controlled trials in adults
Mean Change from Baseline to Endpoint Score
Schizophrenia (dose range 2-30 mg/day)
Bipolar Mania Monotherapy
(dose range 15-30 mg/day)
Bipolar Mania Cotherapy
(dose range 15-30 mg/day)
Adjunctive in MDD (dose range 2-20 mg/day)
Aripi- prazole
Placebo
Aripiprazole
Placebo
Aripiprazole
Placebo
Aripiprazole
Placebo
SAS
-0.06
-0.08
0.503
-0.01
0.731
0.07
0.273
0.01
Barnes
0.08
-0.05
0.213
-0.05
0.302
0.11
0.233
0.03
AIMS
-0.441
-0.02
-0.02
-0.06
0.08
-0.10
0.03
0.02
* A negative score indicates improvement.
1 p < 0.01
2 p < 0.05
3 p < 0.001
Table 10: Mean change from baseline to endpoint score on the SAS, Barnes Akathisia Scale, and AIMS from short-term placebo-controlled trials in children and adolescents
Mean Change from Baseline to Endpoint Score
Schizophreniaa
Bipolar I Disorderb
Aripiprazole
Placebo
Aripiprazole
Placebo
10 mg
n=99
30 mg
n=97
n=98
10 mg
n=96
30 mg
n=99
n=94
SAS
0.51
0.32
-0.3
0.62
1.23
-0.1
Barnes
0.1
0.1
0.0
-0.1
0.1
0.0
AIMS
-0.2
-0.1
-0.1
0.0
0.0
0.0 a Six-week schizophrenia trial of adolescent patients age 13-17
b Four-week bipolar I disorder trial of pediatric and adolescent patients age 10-17. SAS mean change for aripiprazole 10 mg/day treatment arm, N=95).
* A negative score indicates improvement.
1 p < 0.01
2 p < 0.05
3 p<0.0001
In a long-term (26-week), placebo-controlled trial in adult patients with schizophrenia, data from the Simpson Angus Rating Scale, the Barnes Akathisia Scale, and the Assessments of Involuntary Movement Scales did not show a difference between aripiprazole and placebo.
Dystonia
Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs. An elevated risk of acute dystonia is observed in males and younger age groups.
Somnolence
Somnolence (including sedation) was a commonly reported adverse event in patients treated with aripiprazole in clinical trials and was reported more frequently in children and adolescents than in adults.
Table 11: Percentage of Adult Patients Reporting Somnolence Adverse Events (including sedation) in Short-Term Placebo-Controlled Trials
Percentage of Patients Reporting Event
Schizophrenia (dose range 2-30 mg/day)
Bipolar Mania Monotherapy
(dose range 15-30 mg/day)
Bipolar Mania Cotherapy
(dose range 15-30 mg/day)
Adjunctive in MDD (dose range 2-20 mg/day)
Aripi-
prazole
Placebo
Aripi
prazole
Placebo
Aripiprazole
Placebo
Aripiprazole
Placebo
Somnolence
9.6
7.7
12.8
6.0
6.3
3.8
9.9
4.6
(including
(89/926)
(32/413)
(117/917)
(45/753)
(16/253)
(5/130)
(54/547)
(25/538)
sedation)
Somnolence (including sedation) led to discontinuation of treatment for (aripiprazole-treated, placebo-treated) 0.1% and 0.2% of adult schizophrenia patients, 0.1% and 0% of adult monotherapy patients with bipolar I disorder, 1.2% and 0% of adjunctive aripiprazole and adjunctive placebo-treated adult patients with bipolar I disorder, and 0.6% and 0% of adjunctive aripiprazole and adjunctive placebo-treated adult patients with major depressive disorder, respectively.
Table 12: Percentage of Children and Adolescent Patients Reporting Somnolence Adverse Events (including sedation) in Short-Term Placebo-Controlled Trials
Percentage of Patients Reporting Event
Schizophrenia a
Bipolar I Disorder b
Aripiprazole
Aripiprazole
10 mg
30 mg
Placebo
10 mg
30 mg
Placebo
Somnolence (including sedation)
12 (12/100)
22 (22/102)
6 (6/100)
21 (21/98)
27 (27/99)
3 (3/97)
a Six-week schizophrenia trial of adolescent patients age 13-17
b Four-week bipolar I disorder trial of pediatric and adolescent patients age 10-17
Somnolence (including sedation) led to discontinuation of treatment for (aripiprazole-treated, placebo-treated) 0.5% and 0% of adolescent patients with schizophrenia and 1.5% and 0% of pediatric and adolescent patients with bipolar I disorder, respectively.
Weight Gain
Adults
In 4- to 6-week trials in adults with schizophrenia, there was a slight difference in mean weight gain between aripiprazole and placebo patients (+0.7 kg vs. 0.05 kg, respectively) and also a statistically significant difference in the proportion of patients meeting a weight gain criterion of ≥7% of body weight [aripiprazole (8%) compared to placebo (3%)].
In 3-week trials in adults with bipolar mania, the mean weight gain for aripiprazole and placebo patients was 0.1 kg vs. 0.0 kg, respectively. The proportion of patients meeting a weight gain criterion of ≥7% of body weight was aripiprazole 2% compared to placebo 3%. In the 6-week trial in mania in which aripiprazole or placebo was used as adjunctive therapy with either lithium or valproate, the mean weight gain for aripiprazole and placebo patients was 0.6 kg vs. 0.2 kg, respectively. The proportion of patients meeting a weight gain criterion of ≥7% of body weight with adjunctive aripiprazole was 3% compared to adjunctive placebo 4%.
In the 6-week trials of aripiprazole adjunctive to antidepressants in patients with MDD, the mean weight gain with adjunctive aripiprazole was 1.6 kg vs. 0.5 kg with adjunctive placebo. The proportion of patients meeting a weight gain criterion of ≥7% of body weight during the 6-week randomization period was 5% with adjunctive aripiprazole compared to 1% with adjunctive placebo.
In a long-term (26-week) placebo-controlled study of aripiprazole in adults with schizophrenia, a categorization of patients with schizophrenia at baseline on the basis of body mass index [BMI< 23 (“low”); 23-27 (“normal”); > 27 (“high”)] revealed mean weight losses in patients treated with aripiprazole and patients on placebo ( “low” BMI, 0.5 kg weight loss in both treatment groups; “normal” BMI, mean weight loss of 1.3 kg in aripiprazole-treated patients and 0.6 kg in placebo-treated patients; “high” BMI, mean weight loss of 2.1 kg in aripiprazole-treated patients and 1.5 kg in placebo-treated patients).
In a long-term (52-week) study of aripiprazole and haloperidol in adults, a categorization of patients with schizophrenia at baseline on the basis of BMI revealed the greatest mean weight gain in patients with low BMI compared to normal or overweight patients in both groups (patients with “low” BMI, mean weight gain 2.6 kg in aripiprazole-treated patients and 1.5 kg in haloperidol-treated patients; “normal” BMI, a mean weight gain of 1.4 kg in aripiprazole-treated patients and 0.2 kg in haloperidol-treated patients; “high” BMI, weight loss of 1.2 kg in aripiprazole-treated patients and 0.8 kg in haloperidol-treated patients).
In both long-term schizophrenia studies, the highest incidence of clinically significant weight gain (>7% of body weight) was in patients with a low BMI (<23) compared to normal (23-27) or overweight patients (>27).
In an open-label longer-term (up to 1 year) trial of aripiprazole adjunctive to antidepressants in patients with MDD, the mean change in body weight from baseline to endpoint (LOCF) was 2.9 kg; at Week 52 (completers), the mean change in weight was 4.0 kg. The proportion of patients with clinically relevant weight gain (≥7% increase from baseline) was 23.3% at endpoint LOCF and 34.3% at Week 52 (completers). The mean BMI at baseline was 31 kg/m2.
Adolescents
Changes in weight in the 6-week, placebo-controlled clinical trial in adolescent patients with schizophrenia and the 4-week placebo-controlled clinical trial in pediatric and adolescent patients with bipolar I disorder are summarized in Table 13.
Table 13: Change in weight (kg) and proportion of patients with ≥ 7%
increase in body weight in acute placebo-controlled trials in children and adolescent patients
Schizophreniaa
Placebo
Aripiprazole
N=100
10 mg
N=100
30 mg
N=102
Weight (kg)
Change from baseline to Last Visit
n=98
-0.8
n=99 0.0
n=97 0.2
Proportion of patients with ≥ 7%
increase from baseline weight at Last Visit
1% (1/98)
4% (4/99)
5.2% (5/97)
Bipolar Disorderb
Placebo
Aripiprazole
N=97
10 mg
N=98
30 mg
N=99
Weight (kg)
Change from baseline to Last Visit
n=92 0.5
n=95 0.6
n=96 0.9
Proportion of patients with ≥ 7% increase from baseline weight at
Last Visit
3.3% (3/92)
3.2% (3/95)
9.4% (9/96)
a Six-week schizophrenia trial of adolescent patients age 13-17
b Four-week bipolar disorder trial of pediatric and adolescent patients age 10-17
There was a mean increase in weight of +2.03 kg from baseline to Week 26 during an uncontrolled, 26-week, flexible dose, open-label extension study of adolescent patients with schizophrenia that completed the 6-week placebo-controlled clinical trial. At Week 26, 26% (47/181) of adolescent patients with schizophrenia had a ≥7% increase in weight from baseline, not adjusted for normal growth (see 7 Warnings and Precautions, Endocrine and Metabolism, Weight, glucose and lipid changes in adolescents with schizophrenia or pediatric and adolescent patients with bipolar I disorder).
In a 26-week placebo-controlled extension study that included adolescent patients with bipolar I disorder (manic or mixed episode) who completed the acute phase 4-week placebo-controlled study, the mean increase in weight at the last study visit was +3.20, +2.85 and +0.98 kg for aripiprazole 10 mg/day aripiprazole, 30 mg/day aripiprazole and placebo, respectively. At the last study visit 35.8% (34/95) and 29.2% (28/96) of patients treated with 10 mg/day aripiprazole or 30 mg/day aripiprazole, respectively, had a ≥7% increase in weight from baseline, compared to 9.8% (9/92) of patients receiving placebo (see 7 Warnings and Precautions, Endocrine and Metabolism, Weight, Glucose and Lipid Changes in Adolescents with Schizophrenia or Pediatric and Adolescent Patients with Bipolar I Disorder).
ECG Changes
Between-group comparisons for a pooled analysis of placebo-controlled trials in adult patients with schizophrenia or bipolar mania, in the acute (4-6 week) placebo-controlled trials in adolescent patients with schizophrenia or bipolar I disorder, or in the 6-week placebo-controlled trials of adjunctive aripiprazole in patients with MDD, revealed no significant differences between oral aripiprazole and placebo in the proportion of patients experiencing potentially important changes in ECG parameters.
In adults aripiprazole was associated with a median increase in heart rate of 2 beats per minute compared to no increase among placebo patients.
In a long-term (52-week) placebo-controlled cotherapy study with lithium and valproate in adult patients with bipolar mania, a change from baseline in QTcF interval > 30 msec was reported for a greater proportion of patients on aripiprazole than on placebo (Table 14). The proportion of patients with QTc intervals >450 msec was similar between both treatment groups (Table 14).
Table 14: Percentage of Adult Patients With Bipolar Mania Reporting a Change from Baseline in QTc Interval
52-Week Cotherapy Study with Lithium and Valproate
Aripiprazole
Placebo
Change > 30 msec
QTcF
13
7
QTcB
17
14
Change > 60 msec
QTcF
2
1
QTcB
3
2
> 450 msec
QTcF
3
3
QTcB
10
8
Additional Findings Observed in Clinical Trials
Adverse Events in Long-Term, Double-Blind, Placebo-Controlled Trials in Adults
The adverse events reported in a 26-week, double-blind trial comparing oral aripiprazole and placebo in adult patients with schizophrenia were generally consistent with those reported in the short-term, placebo-controlled trials, except for a higher incidence of tremor [8% (12/153) for aripiprazole vs. 2% (3/153) for placebo]. In this study, the majority of the cases of tremor were of mild intensity (8/12 mild and 4/12 moderate), occurred early in therapy (9/12 ≤49 days), and were of limited duration (7/12 ≤10 days). Tremor infrequently led to discontinuation (<1%) of aripiprazole. In addition, in a long-term (52-week), active-controlled study, the incidence of tremor for aripiprazole was 5% (40/859).
The adverse event profile for aripiprazole in a long-term (52-week) placebo-controlled cotherapy study with lithium and valproate in adult patients with bipolar mania was generally consistent with what was observed in the short-term bipolar mania studies. Although akathisia was the most common adverse event that led to discontinuation of aripiprazole treatment in the short-term bipolar mania studies, in the long-term cotherapy study depression was the most common adverse event leading to discontinuation of treatment with aripiprazole. Depression adverse events led to withdrawal of 4% of patients in the aripiprazole group and 2% of patients on placebo.
Adverse Events in a 26-Week Open Label Extension Trial in Adolescent Patients with Schizophrenia
The safety profile in adolescent patients (13-17 years of age) with schizophrenia in a 26-week, uncontrolled, open-label extension trial, which included patients that completed the 6-week placebo-controlled trial, was generally similar to that observed in the 6-week, placebo-controlled trial.
Adverse events such as extrapyramidal disorder, somnolence, and tremor were reported at similar frequencies in both the 6-week placebo-controlled trial and during the 26-week open-label extension trial (19.2% extrapyramidal disorder; 13.8% somnolence; 6.3% tremor). The majority of these adverse events observed in the open-label 26-week study had a first onset during that study.
Adverse Events in a 26-Week Extension Trial in Pediatric and Adolescent Patients with Bipolar I Disorder
The safety profile in pediatric and adolescent patients (10-17 years of age) with bipolar I disorder in a 26-week placebo-controlled extension of the four-week acute trial was similar to the safety profile in the acute phase, with the exception of weight gain. In the 4-week acute phase, clinically significant weight gain (≥ 7% increase from baseline) was 6% in patients receiving aripiprazole and 3% in patients receiving placebo. In the acute plus extension phase, clinically significant weight gain was 33% in patients receiving aripiprazole and 10% in patients receiving placebo (see 7 Warnings and Precautions, Endocrine and Metabolism, Weight, Glucose and Lipid Changes in Adolescents with Schizophrenia or Pediatric and Adolescent Patients with Bipolar I Disorder).
Other Adverse Events Observed During the Pre-Marketing Evaluation of Oral Aripiprazole
Following is a list of MedDRA terms that reflect treatment-emergent adverse events as defined in the introduction to the 8 Adverse Reactions section reported by patients treated with oral aripiprazole at multiple doses ≥2 mg/day during any phase of a trial within the database of 13,543 adult patients. All events assessed as possible adverse drug reactions have been included. In addition, medically/clinically meaningful events particularly those that are likely to be useful to the prescriber or that have pharmacologic plausibility, have been included. Events already listed in Tables 2 to 6 or other parts of the 8 Adverse Reactions section have been excluded. Although the events reported occurred during treatment with aripiprazole, they were not necessarily caused by it.
Events are further categorized by MedDRA system organ class and listed in order of decreasing frequency according to the following definitions:
frequent adverse events are defined as those occurring on 1 or more occasions in at least 1/100 patients (only those not already listed in the tabulated results from placebo-controlled trials appear in this listing); infrequent adverse events are those occurring in less than 1/100 but at least 1/1,000 patients; rare events are those occurring in less than 1/1,000.
Adults with schizophrenia or bipolar I disorder
Blood and Lymphatic System Disorders:
Infrequent: leukopenia, neutropenia, thrombocytopenia
Cardiac Disorders:
Infrequent: bradycardia, palpitations, cardiopulmonary failure, myocardial infarction, cardio-respiratory arrest, atrioventricular block, extrasystoles, sinus tachycardia, atrial fibrillation, angina pectoris, myocardial ischemia;
Rare: atrial flutter, supraventricular tachycardia, ventricular tachycardia
Endocrine Disorders:
Infrequent: diabetes mellitus (including blood insulin increased, carbohydrate tolerance decreased, diabetes mellitus non-insulin-dependent, glucose tolerance impaired, glycosuria, glucose urine, glucose urine present), hyperglycemia, hypoglycemia, polydipsia;
Rare: diabetic ketoacidosis, diabetic hyperosmolar coma
Eye Disorders:
Infrequent: photophobia, diplopia, eyelid edema, photopsia
Gastrointestinal Disorders:
Infrequent: gastroesophageal reflux disease, dysphagia, swollen tongue, esophagitis;
Rare: pancreatitis
General Disorders and Administration Site Conditions:
Frequent: asthenia, peripheral edema, irritability, chest pain;
Infrequent: feeling jittery, face edema, thirst, angioedema;
Rare: hypothermia
Hepatobiliary Disorders:
Rare: hepatitis, jaundice
Immune System Disorders:
Infrequent: hypersensitivity
Injury, Poisoning, and Procedural Complications:
Frequent: fall;
Infrequent: self mutilation;
Rare: heat stroke
Investigations:
Frequent: weight decreased;
Infrequent: hepatic enzyme increased (increased ALT, increased AST), blood glucose increased, blood prolactin increased, blood urea increased, electrocardiogram QT prolonged, blood creatinine increased, blood bilirubin increased;
Rare: blood lactate dehydrogenase increased, glycosylated hemoglobin increased, gamma-glutamyl transferase (GGT) increased
Metabolism and Nutrition Disorders:
Infrequent: hyperlipidemia, anorexia, hypokalemia, hyponatremia
Musculoskeletal and Connective Tissue Disorders:
Infrequent: muscle rigidity, muscular weakness, muscle tightness, mobility decreased;
Rare: rhabdomyolysis
Nervous System Disorders:
Frequent: coordination abnormal;
Infrequent: speech disorder, dyskinesia, parkinsonism, memory impairment, cogwheel rigidity, cerebrovascular accident, convulsion, hypokinesia, tardive dyskinesia, hypotonia, myoclonus, hypertonia, akinesia, bradykinesia;
Rare: Grand Mal convulsion, choreoathetosis, neuroleptic malignant syndrome
Psychiatric Disorders:
Frequent: suicidal ideation;
Infrequent: aggression, loss of libido, suicide attempt, hostility, libido increased, anger, anorgasmia, delirium, intentional self injury, completed suicide, tic, homicidal ideation;
Rare: catatonia, sleep walking
Renal and Urinary Disorders:
Infrequent: urinary incontinence, urinary retention, polyuria, nocturia
Reproductive System and Breast Disorders:
Infrequent: menstruation irregular, erectile dysfunction, amenorrhea, breast pain;
Rare: gynaecomastia, priapism
Respiratory, Thoracic, and Mediastinal Disorders:
Frequent: nasal congestion, dyspnea, pneumonia aspiration
Skin and Subcutaneous Tissue Disorders:
Frequent: rash (including erythematous, exfoliative, generalized, macular, maculopapular, papular rash; acneiform, allergic, contact, exfoliative, seborrheic dermatitis, neurodermatitis, and drug eruption), hyperhydrosis;
Infrequent: pruritus, photosensitivity reaction, alopecia, urticaria
Vascular Disorders:
Frequent: hypertension;
Infrequent: hypotension, syncope
Adolescent schizophrenia patients (13-17 years of age)
Most adverse reactions observed in the pooled database of 281 adolescent patients aged 13-17 years were also observed in the adult population (see Tables 3 and 4; 8.2 Clinical Trial Adverse Reactions, Other Adverse Events Observed During the Pre-Marketing Evaluation of Oral Aripiprazole, Adults with schizophrenia or bipolar I disorder). Additional adverse reactions observed in the adolescent population are listed below.
General Disorders and Administration Site Conditions:
Infrequent: feeling abnormal
Metabolism and Nutrition Disorders:
Infrequent: hypertriglyceridemia
Nervous System Disorders:
Infrequent: sleep talking
Respiratory, Thoracic, and Mediastinal Disorders:
Frequent: rhinorrhea
Skin and Subcutaneous Tissue Disorders:
Infrequent: hirsutism
See also 8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Pediatric and adolescent patients (10-17 years of age) with bipolar I disorder
Most adverse reactions observed in the pooled database of 233 pediatric and adolescent patients with bipolar I disorder aged 10-17 years were also observed in the adult population. Additional adverse reactions observed in the pediatric and adolescent population are listed below.
Gastrointestinal Disorders:
Infrequent: tongue dry, tongue spasm
Infections and Infestations:
Frequent: upper respiratory tract infection
Investigations:
Frequent: blood insulin increased
Nervous System Disorders:
Infrequent: drooling
Respiratory, Thoracic, and Mediastinal Disorders:
Frequent: rhinorrhea
See also 8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Adjunctive to antidepressants in adult MDD patients
Most adverse events observed in the pooled short-term trials of aripiprazole adjunctive to antidepressants in MDD patients were also observed in the aripiprazole trials in schizophrenia and bipolar I disorder. Additional adverse events observed in the adult MDD population with higher incidence in adjunctive aripiprazole-treated patients compared to adjunctive placebo-treated patients are listed below.
Ear and Labyrinth Disorders:
Infrequent: vertigo
Gastrointestinal Disorders:
Infrequent: abdominal distension
Psychiatric Disorders:
Frequent: bruxism
Skin and Subcutaneous Tissue Disorders:
Infrequent: increased tendency to bruise
8.2.1. Clinical Trial Adverse Reactions – Pediatrics
Only specific adverse reactions of glucose, lipid and prolactin changes in pediatric and adolescent patients are included in this section. See 8.2 Clinical Trial Adverse Reactions for all other clinical trial adverse reactions in pediatric and adolescent patients.
Glucose
In the 4- and 6-week placebo-controlled clinical trials with pediatric and adolescent patients with bipolar I disorder and adolescent schizophrenia patients, respectively, there were no patients with fasting serum glucose levels that shifted from normal baseline to clinically significant high values (<5.55 mmol/L to ≥6.99 mmol/L) at endpoint in any treatment group. In these studies, fasting glucose data were from approximately 50 patients per treatment group. Therefore, these data cannot be considered entirely predictive of the effects of aripiprazole on glucose metabolism during use in adolescent patients with schizophrenia and pediatric and adolescent patients with bipolar I disorder. In a 26-week open-label extension trial that included adolescent patients with schizophrenia and pediatric and adolescent patients with bipolar I disorder treated with aripiprazole, a shift from normal to high fasting glucose at Week 26 was reported for 1.9% (3/155) of the adolescent schizophrenia patients and none (0/42) of the pediatric and adolescent patients with bipolar I disorder.
There was a mean increase of +0.12 mmol/L in fasting glucose at Week 26 during the 26-week uncontrolled, open-label extension study in adolescent schizophrenia patients (n=166, mean baseline 4.87 mmol/L) and in pediatric and adolescent patients with bipolar I disorder (n=44, mean baseline 4.75 mmol/L) (see 7 Warnings and Precautions, Endocrine and Metabolism, Weight, Glucose and Lipid Changes in Adolescents with Schizophrenia or Pediatric and Adolescent Patients with Bipolar I Disorder).
Lipids
Table 15 shows the proportion of pediatric and adolescent patients with changes in total cholesterol, fasting triglycerides and fasting HDL cholesterol in 4- and 6-week placebo-controlled trials pediatric and adolescent patients (10-17 years) with bipolar I disorder and in adolescent patients (13-17 years) with schizophrenia, respectively, and the 26-week uncontrolled, open-label extension trial that included both patient populations. In the 4- and 6-week placebo-controlled clinical trials lipid data were from approximately 30 to 50 patients per treatment group. Therefore, these data cannot be considered entirely predictive of the effects of aripiprazole on lipid metabolism during use in adolescent patients with schizophrenia and pediatric and adolescent patients with bipolar I disorder.
Table 15: Changes in Blood Lipid Parameters in Pediatric and Adolescent Patientsa
Adolescent Patients with Schizophrenia
Category Change (at least once) from Baseline
Trial Type and Duration
Treatment Arm
n/N
%
10 mg Aripiprazole
3.8
Total Cholesterol
Normal to High
(<4.40 mmol/L to ≥ 5.17 mmol/L)
6-week placebo-
controlled trial
30 mg Aripiprazole
1.9
Placebo
0.0
26-week open-label
trial
Aripiprazole
3
10 mg Aripiprazole
0.0
Fasting Triglycerides
Normal to High
(<1.70 mmol/L to ≥ 2.26 mmol/L)
6-week placebo-
controlled trial
30 mg Aripiprazole
0.0
Placebo
0.0
26-week open-label
trial
Aripiprazole
0.0
Table 15: Changes in Blood Lipid Parameters in Pediatric and Adolescent Patientsa
10 mg Aripiprazole
14.7
Fasting HDL
Normal to low
(>1.03 mmol/L ≤1.03 mmol/L)
6-week placebo-
controlled trial
30 mg Aripiprazole
7.1
Placebo
33.3
26-week open-label trial
Aripiprazole
7.2
Pediatric and Adolescent Patients with Bipolar I Disorder
Category Change (at least once) from Baseline
Trial Type and Duration
Treatment Arm
n/N
%
10 mg Aripiprazole
0.0
Total Cholesterol
Normal to High
(<4.40 mmol/L to ≥ 5.17 mmol/L)
4-week placebo- controlled trial
30 mg Aripiprazole
0.0
Placebo
0.0
26-week open-label trial
Aripiprazole
0.0
Fasting Triglycerides
Normal to High
(<1.70 mmol/L to ≥ 2.26 mmol/L)
10 mg Aripiprazole
2.0
4-week placebo-
controlled trial
30 mg Aripiprazole
4.0
Placebo
7.0
26-week open-label trial
Aripiprazole
0.0
10 mg Aripiprazole
4.1
Fasting HDL
Normal to low
(>1.03 mmol/L ≤1.03 mmol/L)
4-week placebo-
controlled trial
30 mg Aripiprazole
5.6
Placebo
7.5
26-week open-label trial
Aripiprazole
10.3 a Incidence rates are the number of patients with baseline values within the specified range and evaluated for the given lab test at Week 6 for adolescent schizophrenia patients, Week 4 for pediatric and adolescent patients with bipolar I disorder.
During the 26-week, uncontrolled, open-label extension study, there were mean decreases in total cholesterol (fasting and nonfasting) at Week 26 in adolescent schizophrenia patients (n=176, mean baseline 3.81 mmol/L; mean decrease -0.0013 mmol/L) and in pediatric and adolescent patients with bipolar I disorder (n= 56, mean baseline 4.21 mmol/L; mean decrease - 0.0088 mmol/L). There were mean decreases in fasting triglycerides at Week 26 in adolescent schizophrenia patients (n=97, mean baseline 1.19 mmol/L; mean decrease -0.12 mmol/L) and in pediatric and adolescent patients with bipolar I disorder (n= 31, mean baseline 1.13 mmol/L; mean decrease -0.04 mmol/L). There was a mean increase in fasting HDL cholesterol at Week 26 in adolescent schizophrenia patients (n=97, mean baseline 1.23 mmol/L; mean increase +0.015 mmol/L), and a mean decrease at Week 26 in pediatric and adolescent patients with bipolar I disorder (n= 31, mean baseline 1.44 mmol/L; mean decrease - 0.06 mmol/L) (see 7 Warnings and Precautions, Endocrine and Metabolism, Weight, Glucose and Lipid Changes in Adolescents with Schizophrenia or Pediatric and Adolescent Patients with Bipolar I Disorder).
Prolactin
In the 6-week placebo-controlled clinical trial in adolescents (13-17 years of age) with schizophrenia, there was a greater incidence of low serum prolactin levels in males (< 86.96 pmol/L) and females (< 130.434 pmol/L) treated with aripiprazole compared to placebo. Low serum prolactin levels were reported for 38.6% (17/44), 31.7% (19/60) and 7% (4/57) of males that received 10 mg/day aripiprazole, 30 mg/day aripiprazole or placebo, respectively. Low serum prolactin levels were reported for 29.6% (16/54), 17.1% (6/35) and 10.3% (4/39) of females that received 10 mg/day aripiprazole, 30 mg/day aripiprazole or placebo, respectively.
In the acute phase 4-week double-blind placebo-controlled trial of aripiprazole in pediatric and adolescent patients (10-17 years of age) in a manic or mixed episode of bipolar I disorder, the incidence of low prolactin levels for males (<86.96 pmol/L) was 40.0%, 45.5% and 4.3% for patients treated with 10 mg/day aripiprazole, 30 mg/day aripiprazole or placebo, respectively. In females, the incidence of low prolactin levels (<130.43 pmol/L) was 9.5%, 33.3% and 0% for patients treated with 10 mg/day aripiprazole, 30 mg/day aripiprazole or placebo, respectively.
During a 26-week open-label study of aripiprazole in adolescent schizophrenic and pediatric and adolescent bipolar I patients manic or mixed phase, there was a mean decrease in prolactin levels (-27.83 pmol/L) relative to baseline (274.78 pmol/L). The overall incidence of low prolactin (as defined above) was greater for patients with bipolar I disorder (45.8%) compared to patients with schizophrenia (34.8%).
The clinical significance of low prolactin levels in adolescence is not known. However, animal studies and case reports suggest a possible association between significantly low prolactin levels and failure to lactate, menstrual cycle disruption, and pubertal development.
8.3. Less Common Clinical Trial Adverse Reactions
See 8.2 Clinical Trials Adverse Reactions, Other Adverse Events Observed During the Pre-Marketing Evaluation of Oral Aripiprazole.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Between-group comparisons for 3- to 6-week, placebo-controlled trials in adult patients with bipolar mania or schizophrenia, a 6-week placebo-controlled trial in adolescent patients with schizophrenia (13-17 years of age) and a 4-week placebo-controlled trial in pediatric and adolescent patients with bipolar I disorder (10-17 years of age) revealed no differences between the aripiprazole and placebo groups in the proportions of patients experiencing clinically important changes in most routine serum chemistry, hematology, or urinalysis parameters (including changes in fasting glucose, triglyceride, HDL, LDL and total cholesterol measurements) with the exception of prolactin. Low prolactin levels were reported more frequently in adolescents treated with aripiprazole than with placebo (see 8.2.1 Clinical Trials Adverse Reactions – Pediatrics).
Similarly, there were no differences in the incidence of discontinuations for changes in serum chemistry, hematology, or urinalysis.
In the 6-week trials of aripiprazole as adjunctive therapy for major depressive disorder, there were no clinically important differences between the adjunctive aripiprazole-treated and adjunctive placebo-treated patients in the median change from baseline in fasting glucose, HDL, LDL, or total cholesterol measurements. The median % change from baseline in fasting triglycerides was 6% for adjunctive aripiprazole-treated patients vs. 0% for adjunctive placebo-treated patients. The incidence of treatment-emergent results of potential clinical relevance during the 6-week randomization period in the pooled studies was similar between the treatment groups except for non-fasting triglycerides (20% adjunctive aripiprazole vs. 13% adjunctive placebo). The median % change from baseline in prolactin was a -12.5% decrease for adjunctive aripiprazole-treated patients and 0% for adjunctive placebo-treated patients. The incidences of treatment-emergent potentially clinically significant abnormally high prolactin (>ULN) were 6.6% on adjunctive aripiprazole and 5.3% on adjunctive placebo.
In a long-term (26-week), placebo-controlled trial in adult patients with schizophrenia and in a 52-week placebo-controlled trial in adult patients with bipolar I disorder who received aripiprazole as cotherapy with lithium or valproate there were no clinically important differences between the aripiprazole and placebo patients in the mean change from baseline in prolactin, fasting glucose, triglyceride, HDL, LDL, and total cholesterol measurements. A similar profile, with the exception of prolactin, was observed in a 26-week placebo-controlled extension phase in pediatric and adolescent patients (10-17 years) with bipolar I disorder (see 7 Warnings and Precautions, Endocrine and Metabolism and 8.2.1 Clinical Trial Adverse Reactions - Pediatrics).
In an open-label longer-term (up to 1 year) trial of aripiprazole adjunctive to antidepressants in patients with MDD, the most frequently (>10% of patients) reported potentially clinically relevant laboratory abnormalities were high prolactin (14%), fasting glucose (14%), fasting total cholesterol (35%), fasting LDL cholesterol (24%), fasting triglycerides (64%), and hemoglobin A1c (8%). For these laboratory parameters, a shift analysis was conducted. The shifts from normal to high were 114/1106 (10.3%) for prolactin, 44/906 (4.9%) for fasting glucose, 135/697 (19.4%) for fasting total cholesterol, 103/784 (13.1%) for fasting LDL cholesterol, 142/741 (19.2%) for fasting triglycerides, and 85/1079 (7.9%) for hemoglobin A1c.
Higher percentages of elevated creatine phosphokinase were observed in aripiprazole-treated adult patients compared to placebo-treated patients in short-term and long-term clinical trials. The most common AEs that were temporally associated with elevated CPK levels were musculoskeletal stiffness, myalgia, chest pain, fall, and muscle rigidity.
8.5. Post-Market Adverse Reactions
The following adverse events were reported during the post-marketing use of aripiprazole. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders:
Leukopenia/neutropenia and agranulocytosis: In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including aripiprazole. Agranulocytosis has also been reported. Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting SOLUFY and then periodically throughout treatment (see 7 Warnings and Precautions, Hematologic and 7 Warnings and Precautions, Monitoring and Laboratory Tests).
Cardiac Disorders:
As with other antipsychotics, sudden death, torsades de pointes, ventricular tachycardia, arrhythmia, cardiopulmonary arrest and QT prolongation have been reported during treatment with aripiprazole. These events during aripiprazole treatment have been very rare or isolated. Many of the patients had pre-existing cardiovascular disease, were on concomitant medications known to prolong the QT interval, had risk factors for QT prolongation, took an overdose of aripiprazole, and/or were morbidly obese. Very rarely, QT prolongation has been reported in the absence of confounding factors.
Eye Disorders:
Oculogyric crisis
Hepatobiliary Disorders:
Hepatic failure
Immune System Disorders:
Rare: Allergic reaction (e.g., anaphylactic reaction, angioedema, laryngospasm, oropharyngeal spasm)
Investigations:
Rare: Blood glucose fluctuation
Nervous System Disorders:
Very rare: Restless legs syndrome
Serotonin toxicity: Isolated cases of serotonin toxicity (also called serotonin syndrome) have been reported with the concomitant use of aripiprazole and serotonergic drugs such as Serotonin-Norepinephrine Reuptake Inhibitors (SNRIs) and Selective Serotonin Reuptake Inhibitors (SSRIs).
Psychiatric Disorders:
Hypersexuality, impulse-control disorders, pathological gambling
Complex sleep-related behaviours: Complex sleep-related behaviours such as somnambulism and sleep-related eating disorder have been associated with the use of atypical antipsychotic drugs, including aripiprazole.
Respiratory, Thoracic and Mediastinal Disorders:
Sleep apnea: Atypical antipsychotic drugs, including aripiprazole, have been associated with cases of sleep apnea, with or without concomitant weight gain. In patients who have a history of or are at risk for sleep apnea, aripiprazole should be prescribed with caution.
Skin and Subcutaneous Tissue Disorders:
Rare: Drug reaction with eosinophilia and systemic symptoms (DRESS)
9. Drug Interactions
9.2 Drug Interactions Overview
Both CYP3A4 and CYP2D6 are responsible for aripiprazole metabolism. Inducers of CYP3A4 can cause an increase in aripiprazole clearance and lower blood levels. Inhibitors of CYP3A4 or CYP2D6 can inhibit aripiprazole elimination and cause increased blood levels. CYP2D6 metabolizing capacity should be considered when aripiprazole is co-administered with drugs that inhibit CYP2D6. See 9.4 Drug-Drug Interactions and 10.3 Pharmacokinetics.
Aripiprazole does not inhibit or induce the CYP2D6 pathway. Aripiprazole is not a substrate of CYP1A1, CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, or CYP2E1 enzymes. Aripiprazole also does not undergo direct glucuronidation. This suggests that an interaction of aripiprazole with inhibitors or inducers of these enzymes, or other factors, like smoking, is unlikely.
Due to its alpha-1 adrenergic receptor antagonist activity, aripiprazole has the potential to enhance the effect of certain antihypertensive agents.
Given the primary CNS effects of aripiprazole, as with most psychoactive medications, combination use of aripiprazole with other CNS drugs with overlapping undesirable effects, such as sedation or orthostatic hypotension, should be avoided (see 9.4 Drug-Drug Interactions).
9.3 Drug-Behaviour Interactions
Alcohol
Given the primary CNS effects of aripiprazole, as with most psychoactive medications, combination use of aripiprazole with alcohol should be avoided.
Smoking
Aripiprazole is metabolised by multiple pathways involving the CYP2D6 and CYP3A4 enzymes but not CYP1A enzymes. Thus, no dosage adjustment is required for smokers.
Cannabis use
The interaction of aripiprazole with individual behavioural risks such as cannabis use has not been studied.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 16 – Established or Potential Drug-Drug Interactions
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
| Strong CYP2D6 inhibitors (e.g., quinidine, fluoxetine, paroxetine) | CT | Co-administration of quinidine (166 mg/day for 13 days), a potent inhibitor of CYP2D6, with a 10-mg single dose of aripiprazole increased the AUC of aripiprazole by 107% but decreased the AUC of its active metabolite, dehydro-aripiprazole, by 32%. In a population pharmacokinetic analysis in patients with major depressive disorder, the steady-state plasma concentrations of fluoxetine and norfluoxetine increased by about 18% and 36%, respectively and concentrations of paroxetine decreased by about 27%. | Dosage adjustment of aripiprazole is required when it is co-administered with a strong CYP2D6 inhibitor and when the strong CYP26 inhibitor is withdrawn from the combination therapy (see 4.2 Recommended Dose and Dosage Adjustment). |
| Strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole) | CT | Co-administration of ketoconazole (200 mg/day for 14 days) with a 15-mg single dose of aripiprazole increased the AUC of aripiprazole and its active metabolite by 63% and 77%, respectively. The effects of a higher ketoconazole dose (400 mg/day) or of weaker inhibitors have not been studied. | Dosage adjustment of aripiprazole is required when it is co-administered with a strong CYP3A4 inhibitor and when the strong CYP3A4 inhibitor is withdrawn from the combination therapy (see 4.2 Recommended Dose and Dosage Adjustment). |
| Strong CYP3A4 inducers (e.g., carbamazepine) | CT | Co-administration of carbamazepine (200 mg BID), a potent CYP3A4 inducer, with aripiprazole (30 mg QD) resulted in an approximate 70% decrease in Cmax and AUC values of both aripiprazole and its active metabolite, dehydro-aripiprazole. | Dosage adjustment of aripiprazole is required when it is co-administered with a strong CYP3A4 inducer and when the strong CYP3A4 inducer is withdrawn from the combination therapy (see 4.2 Recommended Dose and Dosage Adjustment). |
| Benzodiazepines (e.g., lorazepam) | CT | The intensity of sedation was greater with the combination of aripiprazole and lorazepam as compared to that observed with aripiprazole alone. The incidence of orthostatic hypotension observed was greater with the combination of aripiprazole and lorazepam as compared to that observed with lorazepam alone. Co-administration of oral lorazepam (2 mg) and oral aripiprazole (15 mg) to healthy subjects (n=24 males; ages 18-43 years old) did not result in clinically important changes in the pharmacokinetics of either drug. | Concomitant use of aripiprazole with other CNS drugs with similar undesirable effects should be avoided. |
| Famotidine | CT | Co-administration of aripiprazole (given in a single dose of 15 mg) with a 40-mg single dose of the H2 antagonist famotidine, a potent gastric acid blocker, decreased the solubility of aripiprazole and, hence, its rate of absorption. The Cmax of aripiprazole and dehydro-aripiprazole, was reduced by 37% and 21%, respectively. The extent of absorption (AUC) of aripiprazole and dehydro-aripiprazole, was reduced by 13% and 15%, respectively. | No dosage adjustment of aripiprazole is required when administered concomitantly with famotidine. |
| Valproate | CT | When valproate (500-1500 mg/day) and aripiprazole (30 mg/day) were co-administered, at steady state the Cmax and AUC of aripiprazole were decreased by 25%. When aripiprazole (30 mg/day) and valproate (1000 mg/day) were co-administered, at steady state there were no clinically important changes in the Cmax or AUC of valproate. | No dosage adjustment of either drug is required when aripiprazole and valproate are administered concomitantly. |
| Lamotrigine | CT | Co-administration of 10 to 30 mg daily oral doses of aripiprazole for 14 days to subjects with bipolar I disorder had no effect on the steady-state pharmacokinetics 100 to 400 mg once daily lamotrigine, a UDP-glucuronosyltransferase 1A4 substrate. | No dosage adjustment of lamotrigine is required if aripiprazole and lamotrigine are administered concomitantly. Dosing recommendations for lamotrigine should be followed closely if valproate is also to be administered. |
| Lithium | CT | Co-administration of therapeutic doses of lithium (1200-1800 mg/day) for 21 days with aripiprazole (30 mg/day) did not result in clinically important changes in the pharmacokinetics of aripiprazole or its active metabolite, dehydro-aripiprazole (Cmax and AUC increased by less than 20%). Co-administration of aripiprazole (30 mg/day) with lithium (900 mg/day) did not result in clinically important changes in the pharmacokinetics of lithium. | No dosage adjustment of either drug is required when aripiprazole and lithium are administered concomitantly. |
Legend: CT = Clinical Trial
Drugs causing QTc prolongation or electrolyte imbalance
If aripiprazole is administered concomitantly with medicinal products known to cause QT prolongation or electrolyte imbalance, caution should be used (see 7 Warnings and Precautions, Cardiovascular, QT Interval and 8.5 Post-Market Adverse Reactions).
Examples of QTc-prolonging drugs may include, but are not limited to: Class Ia antiarrhythmics (e.g., disopyramide), Class III antiarrhythmics (e.g., amiodarone, sotalol), Class Ic antiarrhythmics (e.g., flecainide, propafenone), certain antidepressants (e.g., tricyclic antidepressants such as amitriptyline and imipramine), other antipsychotics (e.g., chlorpromazine, haloperidol), opioids (e.g. methadone), certain antibiotics (e.g., ciprofloxacin), antimalarials (e.g., quinine, chloroquine), tyrosine kinase inhibitors (e.g., sunitinib), histone deacetylase inhibitors (e.g., vorinostat), beta-2 adrenoreceptor agonists (e.g., salmeterol), 5-HT3 receptor antagonists (e.g., ondansetron), and domperidone.
Potential for Aripiprazole to Affect Other Drugs
Aripiprazole is unlikely to cause clinically important pharmacokinetic interactions with drugs metabolized by cytochrome P450 enzymes. In in vivo studies, 10-mg/day to 30-mg/day doses of aripiprazole had no significant effect on metabolism by CYP2D6 (dextromethorphan, venlafaxine), CYP2C9 (warfarin), CYP2C19 (omeprazole, warfarin, escitalopram), and CYP3A4 (dextromethorphan, escitalopram) substrates. Additionally, aripiprazole and dehydro-aripiprazole did not show potential for altering CYP1A2-mediated metabolism in vitro. No dosage adjustment of dextromethorphan, warfarin, omeprazole, escitalopram, or venlafaxine is required when co-administered with SOLUFY.
A population pharmacokinetic analysis in patients with major depressive disorder showed that the steady-state plasma concentrations of sertraline and desmethylsertraline were not substantially changed when sertraline was co-administered with aripiprazole. No dosage adjustment of sertraline is required when co-administered with SOLUFY.
9.5 Drug-Food Interactions
SOLUFY can be administered with or without food (see 10.3 Pharmacokinetics).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been studied.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been identified.
10 Clinical Pharmacology
10.1 Mechanism of Action
The mechanism of action of aripiprazole, as with other drugs having efficacy in schizophrenia, bipolar disorder and as adjunctive to antidepressants in patients with MDD is unknown. It has been proposed that the efficacy of aripiprazole may be mediated through a combination of partial agonist activity at D2 and 5-HT1A receptors and antagonist activity at 5-HT2A receptors; however, the clinical relevance of these interactions has not been established. Actions at receptors other than D2, 5-HT1A and 5-HT2A may explain some of the other clinical effects of aripiprazole (e.g., the orthostatic hypotension observed with aripiprazole may be explained by its antagonist activity at adrenergic alpha1 receptors). The clinical relevance of these receptor interactions with aripiprazole is unknown.
10.2 Pharmacodynamics
Aripiprazole exhibits high affinity for dopamine D2 and D3, serotonin 5-HT1A and 5-HT2A receptors (Ki values of 0.34, 0.8, 1.7, and 3.4 nM, respectively), moderate affinity for dopamine D4, serotonin 5-HT2C and 5-HT7, alpha1-adrenergic and histamine H1 receptors (Ki values of 44, 15, 39, 57, and 61 nM, respectively), and moderate affinity for the serotonin reuptake site (Ki=98 nM). Aripiprazole has no appreciable affinity for cholinergic muscarinic receptors (IC50>1000 nM). Aripiprazole functions as a partial agonist at the dopamine D2 and the serotonin 5-HT1A receptors, and as an antagonist at serotonin 5-HT2A receptor. The clinical relevance of these receptor interactions with aripiprazole is unknown.
10.3 Pharmacokinetics
Preclinical Pharmacokinetics
In rats, concentrations of unchanged aripiprazole in the brain were up to 5-times higher than plasma concentrations. In vitro, aripiprazole bound extensively (99.4 to 99.8%) to proteins in mouse, rat, rabbit, dog, monkey, and human sera.
Clinical Pharmacokinetics
SOLUFY activity is presumably primarily due to the parent drug, aripiprazole, and to a lesser extent, to its major metabolite, dehydro-aripiprazole, which has affinities for D2 receptors similar to the parent drug and represents 40% of the parent drug exposure in plasma. The mean elimination half-lives are about 75 hours and 94 hours for aripiprazole and dehydro-aripiprazole, respectively. Steady-state concentrations are attained within 14 days of dosing for both active moieties. Aripiprazole accumulation is predictable from single-dose pharmacokinetics. At steady state, the pharmacokinetics of aripiprazole are dose-proportional. Elimination of aripiprazole is mainly through hepatic metabolism involving two P450 isozymes, CYP2D6 and CYP3A4.
Absorption
SOLUFY can be administered with or without food. Administration of a 15-mg aripiprazole tablet with a standard high-fat meal did not significantly affect the Cmax or AUC of aripiprazole or its active metabolite, dehydro-aripiprazole, but delayed Tmax by 3 hours for aripiprazole and 12 hours for dehydro-aripiprazole.
SOLUFY:
Aripiprazole is well absorbed when administered orally as the solution. At equivalent doses of 10 mg, the plasma concentrations of aripiprazole from the solution were slightly higher than that from the tablet formulation (see 14.2 Comparative Bioavailability Studies). For a different aripiprazole oral solution, in a relative bioavailability study comparing the pharmacokinetics of 30 mg aripiprazole as the oral solution to 30 mg aripiprazole tablets in healthy subjects, the solution to tablet ratios of geometric mean Cmax and AUC values were 122% and 114%, respectively (see 4.1 Dosing Considerations). The single-dose pharmacokinetics of aripiprazole were linear and dose-proportional between the doses of 5 mg to 30 mg.
Distribution
The steady-state volume of distribution of aripiprazole following intravenous administration is high (404 L or 4.9 L/kg), indicating extensive extravascular distribution. At therapeutic concentrations, aripiprazole and its major metabolite are greater than 99% bound to serum proteins, primarily albumin. In healthy human volunteers administered 0.5 to 30 mg/day aripiprazole for 14 days, there was dose-dependent D2 receptor occupancy. The clinical relevance of this receptor occupancy by aripiprazole is unknown.
Metabolism
Aripiprazole is metabolized primarily by three biotransformation pathways: dehydrogenation, hydroxylation, and N-dealkylation. Based on in vitro studies, CYP3A4 and CYP2D6 enzymes are responsible for dehydrogenation and hydroxylation of aripiprazole, and N-dealkylation is catalyzed by CYP3A4. Aripiprazole is the predominant drug moiety in the systemic circulation. At steady state, dehydro-aripiprazole, the active metabolite, represents about 40% of aripiprazole AUC in plasma.
Elimination
Following a single oral dose of [14C]-labeled aripiprazole, approximately 25% and 55% of the administered radioactivity was recovered in the urine and feces, respectively. Less than 1% of unchanged aripiprazole was excreted in the urine and approximately 18% of the oral dose was recovered unchanged in the feces.
Special Populations and Conditions
- Geriatrics: In formal single-dose pharmacokinetic studies (with aripiprazole given in a single dose of 15 mg), clearance of aripiprazole was 20% lower in geriatric (≥65 years) subjects compared to younger adult subjects (18 to 64 years). However, there was no effect of age in the population pharmacokinetic analysis in schizophrenia patients. Also, the pharmacokinetics of aripiprazole after multiple doses in geriatric patients appeared similar to that observed in young, healthy subjects. (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.4 Geriatrics).
- Sex: Cmax and AUC of aripiprazole and its active metabolite, dehydro-aripiprazole, are 30 to 40% higher in women than in men, and correspondingly, the apparent oral clearance of aripiprazole is lower in women. However, these differences are largely explained by differences in body weight (25%) between men and women. No dosage adjustment is recommended based on gender.
- Genetic polymorphism: Approximately 8% of Caucasians lack the capacity to metabolize CYP2D6 substrates and are classified as poor metabolizers (PM), whereas the rest are extensive metabolizers (EM). PMs have about an 80% increase in aripiprazole exposure and about a 30% decrease in exposure to the active metabolite compared to EMs, resulting in about a 60% higher exposure to the total active moieties from a given dose of aripiprazole compared to EMs. Co-administration of aripiprazole with known inhibitors of CYP2D6, like quinidine in EMs, results in a 112% increase in aripiprazole plasma exposure, and dose adjustment is needed (see 4.2 Recommended Dose and Dosage Adjustment). The mean elimination half-life for aripiprazole is about 75 hours in EMs and 146 hours in PMs.
- Ethnic origin: Although no specific pharmacokinetic study was conducted to investigate the effects of race on the disposition of aripiprazole, population pharmacokinetic evaluation did not demonstrate clinically important race-related differences in the pharmacokinetics of aripiprazole. No dosage adjustment is recommended based on race.
- Hepatic Insufficiency: In a single-dose study (15 mg of aripiprazole) in subjects with varying degrees of liver cirrhosis (Child-Pugh Classes A, B, and C), the AUC of aripiprazole, compared to healthy subjects, increased 31% in mild HI, increased 8% in moderate HI, and decreased 20% in severe HI. None of these differences would require dose adjustment.
Renal Insufficiency: In patients with severe renal impairment (creatinine clearance <30 mL/min), Cmax of aripiprazole (given in a single dose of 15 mg) and dehydro-aripiprazole increased by 36% and 53%, respectively, but AUC was 15% lower for aripiprazole and 7% higher for dehydro-
- aripiprazole. Renal excretion of both unchanged aripiprazole and dehydro-aripiprazole is less than 1% of the dose. No dosage adjustment is required in subjects with renal impairment.
- Smoking: Based on studies utilizing human liver enzymes in vitro, aripiprazole is not a substrate for CYP1A2 and also does not undergo direct glucuronidation. Smoking should, therefore, not have an effect on the pharmacokinetics of aripiprazole. Consistent with these in vitro results, population pharmacokinetic evaluation did not demonstrate any significant pharmacokinetic differences between smokers and nonsmokers. No dosage adjustment is recommended based on smoking status.
11 Storage, Stability, and Disposal
Store between 15-30°C. Solution must be used within 6 months of opening the bottle.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: aripiprazole
Chemical name: 7-[4-[4-(2,3-dichlorophenyl)-1-piperazinyl]butoxy]-3,4-dihydrocarbostyril.
Molecular formula and molecular mass: C23H27Cl2N3O2 and 448.38 g/mol
Structural formula:
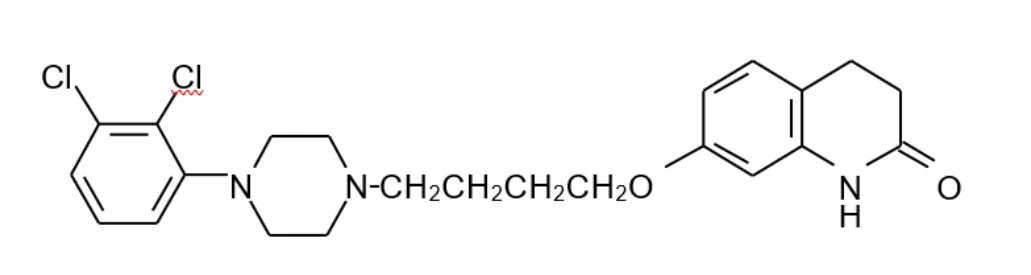
Physicochemical properties: Aripiprazole is a white or almost white crystal or crystalline powder. Aripiprazole is practically insoluble in water, soluble in methylene dichloride and, very slightly soluble in ethanol.
14 Clinical Trials
14.1 Clinical Trials by Indication
Schizophrenia
Adults
The efficacy of aripiprazole in the treatment of schizophrenia was evaluated in five short-term (4- and 6-week), placebo-controlled trials of acutely relapsed inpatients who predominantly met DSM-III/IV criteria for schizophrenia. Four of the five trials were able to distinguish aripiprazole from placebo, but one study, the smallest, did not. Three of these studies also included an active control group consisting of either risperidone (one trial) or haloperidol (two trials), but they were not designed to allow for a comparison of aripiprazole and the active comparators.
Results:
In the four positive trials for aripiprazole, four primary measures were used for assessing psychiatric signs and symptoms. The Positive and Negative Syndrome Scale (PANSS) is a multi-item inventory of general psychopathology used to evaluate the effects of drug treatment in schizophrenia. The PANSS positive subscale is a subset of items in the PANSS that rates seven positive symptoms of schizophrenia (delusions, conceptual disorganization, hallucinatory behavior, excitement, grandiosity, suspiciousness/persecution, and hostility). The PANSS negative subscale is a subset of items in the PANSS that rates seven negative symptoms of schizophrenia (blunted affect, emotional withdrawal, poor rapport, passive apathetic withdrawal, difficulty in abstract thinking, lack of spontaneity/flow of conversation, stereotyped thinking). The Clinical Global Impression (CGI) assessment reflects the impression of a skilled observer, fully familiar with the manifestations of schizophrenia, about the overall clinical state of the patient.
In a 4-week trial (n=414) comparing two fixed doses of aripiprazole (15 or 30 mg/day) and haloperidol (10 mg/day) to placebo, both doses of aripiprazole were superior to placebo in the PANSS total score, PANSS positive subscale, and CGI-severity score. In addition, the 15-mg dose was superior to placebo in the PANSS negative subscale.
In a 4-week trial (n=404) comparing two fixed doses of aripiprazole (20 or 30 mg/day) and risperidone (6 mg/day) to placebo, both doses of aripiprazole were superior to placebo in the PANSS total score, PANSS positive subscale, PANSS negative subscale, and CGI- severity score.
In a 6-week trial (n=420) comparing three fixed doses of aripiprazole (10, 15, or 20 mg/day) to placebo, all three doses of aripiprazole were superior to placebo in the PANSS total score, PANSS positive subscale, and the PANSS negative subscale.
In a 6-week trial (n=367) comparing three fixed doses of aripiprazole (2, 5, or 10 mg/day) to placebo, the 10-mg dose of aripiprazole was superior to placebo in the PANSS total score, the primary outcome measure of the study. The 2-mg and 5-mg doses did not demonstrate superiority to placebo on the primary outcome measure.
In a fifth study, a 4-week trial (n=103) comparing aripiprazole in a range of 5 to 30 mg/day or haloperidol 5 to 20 mg/day to placebo, haloperidol was superior to placebo, in the Brief Psychiatric Rating Scale (BPRS), a multi-item inventory of general psychopathology traditionally used to evaluate the effects of drug treatment in psychosis, and in a responder analysis based on the CGI-severity score, the primary outcomes for that trial. Aripiprazole was only significantly different compared to placebo in a responder analysis based on the CGI-severity score.
Thus, the efficacy of 10-mg, 15-mg, 20-mg, and 30-mg daily doses was established in two studies for each dose. Among these doses, there was no evidence that the higher dose groups offered any advantage over the lowest dose group of these studies.
An examination of population subgroups did not demonstrate any clear evidence of differential responsiveness on the basis of age, gender, or race.
A longer-term trial enrolled 310 inpatients or outpatients meeting DSM-IV criteria for schizophrenia who were, by history, symptomatically stable on other antipsychotic medications for periods of 3 months or longer. These patients were discontinued from their antipsychotic medications and randomized to aripiprazole 15 mg/day or placebo for up to 26 weeks of observation for relapse. Relapse during the double-blind phase was defined as CGI- Improvement score of ≥5 (minimally worse), scores ≥5 (moderately severe) on the hostility or uncooperativeness items of the PANSS, or ≥20% increase in the PANSS total score. Patients receiving aripiprazole 15 mg/day experienced a significantly longer time to relapse over the subsequent 26 weeks compared to those receiving placebo.
Adolescents (13-17 years of age)
The efficacy of aripiprazole in the treatment of schizophrenia was evaluated in one 6-week, placebo-controlled trial that included outpatients, 13-17 years of age, who met DSM-IV criteria for schizophrenia and had a PANSS score ≥ 70 at baseline. The majority of patients included in this trial (75%) were 15-17 years of age. Seventy-four percent of patients had received antipsychotic treatment for previous episodes. In this trial comparing two fixed doses of aripiprazole (10 mg/day, n=100 or 30 mg/day, n=102) to placebo (n=100), aripiprazole was titrated starting from 2 mg/day to the target dose in 5 days in the 10 mg/day treatment arm and in 11 days in the 30 mg/day treatment arm.
Results:
Both doses of aripiprazole were superior to placebo in the PANSS total score, the primary outcome measure of the study. The 30 mg/day dose was not shown to be more efficacious than the 10 mg/day dose. Maintenance of efficacy has not been systematically evaluated in adolescent patients.
Aripiprazole is not indicated for the treatment of schizophrenia in adolescents less than 15 years of age due to insufficient safety and efficacy data (see 1.1 Pediatrics, 7.1.3 Pediatrics and 8 Adverse Reactions).
Bipolar I Disorder
Adults
Acute treatment of manic and mixed episodes
Monotherapy
The efficacy of aripiprazole in the treatment of acute manic episodes was established in four 3-week, placebo-controlled studies in hospitalized patients who met the DSM-IV criteria for bipolar I disorder with manic or mixed episodes. These studies included patients with or without psychotic features and two of the studies also included patients with or without a rapid-cycling course (approximately 20% with rapid cycling course in both studies). Two of these studies included an active control group for assay sensitivity. In the studies that included active control groups, patients were allowed to continue on aripiprazole or active control for up to 12 weeks.
Results:
The primary instrument used for assessing manic symptoms in all four studies was the Young Mania Rating Scale (Y-MRS) an 11-item clinician-rated scale traditionally used to assess the degree of manic symptomatology (irritability, disruptive/aggressive behavior, sleep, elevated mood, speech, increased activity, sexual interest, language/thought disorder, thought content, appearance, and insight) in a range from 0 (no manic features) to 60 (maximum score). The primary efficacy endpoint was the mean change from baseline in total Y-MRS score at the Week 3 endpoint (Last Observation Carried Forward, LOCF). A key secondary endpoint was the Severity of Illness score (mania) from the Clinical Global Impression - Bipolar (CGI-BP) Scale.
In the four studies, patients were randomized to placebo (n=132, n=135, n=165, n=152) or aripiprazole (n=130, n=137, n=155, n=167). Studies with an active control group included a group of patients randomized to haloperidol (n=160) in one study, and a group of patients randomized to lithium (n=165) in the other study.
All four studies evaluated flexible doses of aripiprazole 15 or 30 mg/day, administered once daily (with a starting dose of 15 mg/day in two studies and 30 mg/day in two studies). In all four studies the majority of patients were treated with the 30 mg/day dose.
In all four studies, aripiprazole was superior to placebo in the reduction of manic symptoms, as measured by the mean change from baseline to Week 3 (LOCF) in Y-MRS total score (primary endpoint) and CGI-BP Severity of Illness score (mania) (key secondary endpoint).
Adjunctive Therapy with Lithium or Valproate
The efficacy of adjunctive aripiprazole with concomitant lithium or valproate in the treatment of manic or mixed episodes was established in a 6-week, placebo-controlled study (n=384) with a 2-week lead-in mood stabilizer monotherapy phase in patients who met DSM-IV criteria for bipolar I disorder. This study included patients with manic or mixed episodes and with or without psychotic features.
Results:
Patients were initiated on open-label treatment with lithium or valproate, and remained on stable doses at therapeutic serum levels (lithium 0.6 mEq/L to 1.0 mEq/L; valproate 50 mcg/mL to 125 mcg/mL) for 2 weeks. At the end of 2 weeks, patients demonstrating partial non-response (Y- MRS ≥16) to lithium or valproate were randomized to receive either aripiprazole (n=253) or placebo (n=131) as adjunctive therapy with open-label lithium or valproate. In the 6-week placebo-controlled phase, adjunctive aripiprazole (15 or 30 mg/day, starting dose 15 mg/day) was superior to adjunctive placebo, when each was administered concomitantly with lithium or valproate (at therapeutic serum levels), in the reduction of the Y-MRS total score (primary endpoint) and CGI-BP Severity of Illness score (mania) (key secondary endpoint).
Maintenance treatment
Adjunctive Therapy with Lithium or Valproate
A longer-term trial was conducted in patients meeting DSM-IV criteria for bipolar I disorder with a recent manic or mixed episode. Patients were initiated on open-label lithium (0.6 mEq/L to 1.0 mEq/L) or valproate (50 mcg/mL to 125 mcg/mL) at therapeutic serum levels, and remained on stable doses for 2 weeks. At the end of 2 weeks, patients demonstrating partial non-response (Y-MRS total score ≥16 and ≤35% improvement on the Y-MRS total score) to lithium or valproate while at therapeutic serum levels, received aripiprazole as adjunctive therapy with open-label lithium or valproate. The starting dose of aripiprazole during the stabilization period was 15 mg/day and the dose could be increased to 30 mg/day or decreased to 10 /mg/day beginning on Day 4. Lithium and valproate doses could only be adjusted to maintain therapeutic serum levels or to manage tolerability issues (within therapeutic serum level ranges). Patients on the combination of single-blind aripiprazole and lithium or valproate were required to maintain stability (Y-MRS and MADRS total scores ≤12) for 12 consecutive weeks to be eligible for randomization in the placebo-controlled, double-blind phase of the study.
Results:
Three hundred and thirty-seven patients meeting the criteria for maintained stability were randomized to double-blind treatment with either the same dose of aripiprazole they were on at the end of the stabilization period or placebo plus lithium or valproate. Patients were monitored for manic, mixed or depressive relapse for up to 52 weeks. The primary endpoint was the time from randomization to relapse to any mood event, with mood event defined as hospitalization for a manic, mixed or depressive episode, study discontinuation due to lack of efficacy accompanied by Y-MRS score >16 and/or a MADRS >16, or a serious adverse event of worsening disease accompanied by Y-MRS score >16 and/or a MADRS >16. Aripiprazole was superior to placebo on the primary endpoint.
Pediatric and Adolescent (10-17 years of age)
Acute treatment of manic and mixed episodes
Monotherapy
The efficacy of aripiprazole in the acute treatment of manic or mixed episodes in bipolar I disorder in patients 10-17 years of age was evaluated in one four-week placebo-controlled trial (n=296) of outpatients who met DSM-IV criteria for a manic or mixed episode in bipolar I disorder and had a Y-MRS score ≥20 at baseline. The majority (63%) of patients were 13 years of age or older. This double-blind, placebo-controlled trial compared two fixed doses of aripiprazole (10 mg/day or 30 mg/day) to placebo. The aripiprazole dose was started at 2 mg/day, which was titrated to 5 mg/day after 2 days, and to the target dose in 5 days in the 10 mg/day treatment arm and in 13 days in the 30 mg/day treatment arm.
Results:
Both doses of aripiprazole were superior to placebo in change from baseline to week 4 on the Y-MRS total score, the primary outcome measure of the study. Maintenance of efficacy has not been systematically evaluated in adolescent patients.
Aripiprazole is not indicated for the treatment of manic or mixed episodes in bipolar I disorder in adolescents less than 13 years of age due to insufficient safety and efficacy data (see 1.1 Pediatrics, 7.1.3 Pediatrics and 8 Adverse Reactions).
Adjunctive Treatment of Major Depressive Disorder (MDD)
Adults
The efficacy of aripiprazole in the adjunctive treatment of major depressive disorder was demonstrated in three short-term (6-week), placebo-controlled trials in adult patients meeting DSM-IV criteria for MDD who had an inadequate response to prior antidepressant therapy (1 to 3 courses) in the current episode and who had also demonstrated an inadequate response to 8 weeks of prospective antidepressant therapy (paroxetine controlled-release, venlafaxine extended-release, fluoxetine, escitalopram, or sertraline). Inadequate response for prospective treatment was defined as less than 50% improvement on the 17-item version of the Hamilton Depression Rating Scale (HAMD-17), minimal HAMD-17 score of 14, and a Clinical Global Impressions Improvement rating of no better than minimal improvement. Inadequate response to prior treatment was defined as less than 50% improvement as perceived by the patient after a minimum of 6 weeks of antidepressant therapy at or above the minimal effective dose.
The primary instrument used for assessing depressive symptoms was the Montgomery-Asberg Depression Rating Scale (MADRS), a 10-item clinician-rated scale used to assess the degree of depressive symptomatology (apparent sadness, reported sadness, inner tension, reduced sleep, reduced appetite, concentration difficulties, lassitude, inability to feel, pessimistic thoughts, and suicidal thoughts).
The key secondary instrument was the Sheehan Disability Scale (SDS), a 3-item self-rated instrument used to assess three domains of functioning (work/school, social life, and family life) with each item scored from 0 (not at all) to 10 (extreme).
The mean MADRS total score at baseline was between 25 and 27. SDS total score at baseline was between 5.1 and 5.9.
Results:
In all three trials (n=381, n=362, n=349), aripiprazole was superior to placebo in reducing mean MADRS total scores. In one study, aripiprazole was also superior to placebo in reducing the mean SDS score.
In these trials, patients received aripiprazole adjunctive to antidepressants at a starting dose of 5 mg/day. Based on tolerability and efficacy, doses could be adjusted by 5 mg increments, one week apart. Allowable doses were: 2 mg/day, 5 mg/day, 10 mg/day, 15 mg/day, and for patients who were not on potent CYP2D6 inhibitors fluoxetine and paroxetine, 20 mg/day. All patients who tolerated the initial dose were titrated to at least 10 mg/day. The mean final dose at the end point for the three trials was 10.7 mg/day, 11.4 mg/day, and 10.7 mg/day.
An examination of population subgroups did not reveal evidence of differential response based on age, choice of prospective antidepressant, or race. With regard to gender, a smaller mean reduction on the MADRS total score was seen in males than in females. The statistical significance of the treatment-by-gender effect in the combined analysis is primarily due to the results of one of 3 studies. Consistent results between males and females were reported in 2 of the 3 studies. The clinical relevance of this apparent treatment-by-gender is unknown.
Clinical trials evaluating aripiprazole in MDD did not include aripiprazole monotherapy treatment arms. It is therefore unknown whether efficacy in adjunct treatment is due to aripiprazole alone or from combined treatment with an ADT.
14.2 Comparative Bioavailability Studies
A randomized, balanced, open-label, two-treatment, two-period, two-sequence, single-dose (10 mg dose), crossover, bioequivalence study of PrSOLUFY, 1 mg / mL solution (Orimed Pharma Inc.) and PrABILIFY®, 10 mg tablets (Otsuka Canada Pharmaceutical Inc.) was conducted in healthy, adult male subjects under fasting conditions. Comparative bioavailability data from 29 subjects that were included in the statistical analysis are presented in the following table:
Table 17 – Summary Table of the Comparative Bioavailability Data
Aripiprazole (1 x 10 mg) Geometric mean Arithmetic mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of geometric means | 90% Confidence Interval |
AUC723 (ng·h / mL) | 1845.32 1875.83 (19.29) | 1718.38 1747.64 (19.58) | 107.4 | 102.4 - 112.6 |
Cmax (ng / mL) | 52.17 53.51 (22.12) | 46.21 47.65 (26.33) | 112.9 | 104.9 - 121.5 |
Tmax4 (h) | 2.50 (1.00 - 8.00) | 3.05 (1.00 - 8.00) | ||
1 PrSOLUFY, 1 mg / mL, solution (Orimed Pharma Inc.)
2 PrABILIFY® aripiprazole tablets, 10 mg tablets (Otsuka Canada Pharmaceutical Inc.)
3 n=29
4Expressed as the median (range) only.
Due to the long elimination half-life of Aripiprazole, AUCI and T1/2 could not be accurately calculated from the data obtained in this study.
15. Microbiology
Not Applicable
16. Non-Clinical Toxicology
General Toxicology
Acute Toxicity
The acute oral toxicity of aripiprazole was determined in rats and monkeys. The estimated median lethal oral dose in male and female rats was 953 and 705 mg / kg, respectively, and in monkeys was greater than 2000 mg/kg for both sexes. Clinical signs consistent with pharmacologically mediated central nervous (CNS) depression and extrapyramidal side effects were noted in both species. In rats, clinical signs included decreased spontaneous motor activity, crouching, prone position, ataxia, tremors, convulsions, straub tail, catalepsy, ptosis, and coldness to touch. In monkeys, principal drug-related effects included impaired motor activity, hyporeactivity to external stimuli, tremors, catalepsy, closed eyes, crouching, and prone and/or lateral position.
In single-dose intravenous studies in rats, dehydro-aripiprazole produced clinical effects similar to those observed at high single oral doses of parent drug, whereas metabolite OPC-3373 produced no drug-related toxicity.
Short- and Long-Term Toxicity
The short- and long-term toxicity of aripiprazole was determined in 4- to 52-week oral toxicity studies in rats and monkeys. The results from these studies are summarized in the following table.
Table 18 - Short- and Long-Term Toxicity
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
Rat/SD
Oral gavage
4 weeks
0, 60, 100
10 or 15 M
10 or 15 F
60 and 100 mg/kg/day: Sedation (primarily in Week 1) and dose-related decreases in body weight, body weight gain, and food consumption; dose-related minimal or mild increases in serum glutamic pyruvic transaminase, glutamic oxaloacetic transaminase, and gamma-glutamyltranspeptidase; and microscopically, dose-related minimal to moderate adrenocortical hypertrophy, mild atrophy of the pars intermedia in the pituitary gland, minimal to mild bone marrow hypocellularity, increased incidence and severity of pulmonary alveolar foam cell accumulation in the lung, minimal salivary gland acinar cell hypertrophy, minimal mammary gland lobular hyperplasia with minimal to mild milk secretion, minimally decreased numbers of ovarian corpora lutea, and low incidences of minimal uterine atrophy.
100 mg/kg/day: Emaciation, transient hypothermia, lacrimation, tremors, and unkempt appearance and microscopically, minimal mucification of the vaginal epithelium.
All mammary gland and reproductive tract changes in females were considered to be secondary to aripiprazole-related increases in serum prolactin. Additionally, all changes were reversible or partially reversible after a 4-week post-dose period for the 100 mg/kg/day animals.
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
Rat/SD
Oral gavage
13 weeks
0, 2, 6, 20
10 or 16 M
10 or 16 F
2 and 6 (M) mg/kg/day: No drug-related changes.
6 (F) and 20 mg/kg/day: In females, minimal increases in body weight gain and food consumption (6 mg/kg/day only) and microscopically, mucification of vaginal epithelium and lobular hyperplasia of the mammary glands.
20 mg/kg/day: Minimal decreases in body weight gain and food consumption in males; decreased liver and uterus weights; and microscopically, mammary milk secretion in females. Anatomic changes in the mammary gland and reproductive tract of females were considered to be secondary to aripiprazole-related increases in serum prolactin. At the end of the 4-week post-dose period, all findings were reversible except for minimal decreases in body weight gain and food consumption.
Rats/SD
Oral gavage
26 weeks
0, 10, 30,
60
20 or 25 M
20 or 25 F
10 mg/kg/day: Minimal or mild increases in body weight and food consumption in females.
10, 30, and 60 mg/kg/day: Dose-related minimal to moderate decreases in body weight (10 mg/kg/day only in males), including initial weight loss at 60 mg/kg/day; minimal or mild decreases in serum total protein and albumin; pale discoloration of the lungs; and microscopically, dose- related minimal to moderate atrophy of pituitary pars intermedia, increased incidence of minimal to moderate pulmonary histiocytosis, and changes in the mammary gland (atrophy in males ≥30 mg/kg/day; hyperplasia in females) and female reproductive tract (ie, persistent diestrus) that were considered secondary to drug-related hyperprolactinemia.
30 and 60 mg/kg/day: Dose-related increased incidences of transient post-dose hypoactivity and ptosis and predose hyperactivity; minimal to moderate decreases in food consumption; and microscopically, minimally increased adrenocortical lipofuscin pigment and minimal to mild
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
adrenocortical hypertrophy in females.
60 mg/kg/day: Minimal decreases in hematocrit, reticulocytes, and hemoglobin (females); increased adrenal (females) and lung weights; decreased testicular size and weight; dark discoloration of the adrenals and ovaries; and, microscopically, minimal to moderate bilateral testicular atrophy and minimally increased ovarian lipofuscin pigment.
Except for remnants of the adrenal and ovarian pigment, all aripiprazole- related effects were reversible or partially reversible (hyperactivity and pulmonary histiocytosis with associated increases in lung weight) after a 13-week post-dose period.
Rat/SD
Oral gavage
52 weeks
0, 1, 3, 10
20 M
20 F
1, 3, and 10 mg/kg/day: Mild to moderate uterine atrophy and slight increase in corpora lutea.
3 and 10 mg/kg/day: Minimal to mild increases (transient at 10 mg/kg/day) in body weights; minimal, sporadic increases in food consumption; decreases in adrenal, liver, kidney, and uterus weights and increases in ovarian weights; and microscopically, increased severity of lobular hyperplasia of mammary gland and increased incidence and severity of vaginal epithelial mucification in females (changes considered secondary to aripiprazole-related increases in prolactin).
10 mg/kg/day: Decreased liver weight; macroscopic evidence of mammary gland development in females; and microscopically, karyomegaly of hepatocytes, renal proximal tubular epithelium, and Harderian gland acinar cells.
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
Monkey/ Cynomolgus
Oral Gavage
4 weeks
1, 5, 25,
125
1 M
1 F
1, 5, 25, and 125 mg/kg/day: Impairment of motor activity characterized by ataxic gait, reduced motor activity, and/or absence of motion (1 mg/kg/day only in Week 1).
5, 25, and 125 mg/kg/day: Closed eyes, catalepsy, tremors, and slight decreases in food consumption (Weeks 1 and 2).
25 and 125 mg/kg/day: Abnormal posture (crouching, lateral, or prone position) and hyporeactivity; minimal dose-related body weight loss (Weeks 1 and 2); and at necropsy, retention of gallsand (granular material) in the gallbladder.
125 mg/kg/day: At necropsy, a stone (calculus) in the gallbladder of 1 animal.
Monkey/ Cynomolgus
Oral Gavage
13 weeks
0, 0.5, 1,
5, 25
3 to 5 M
3 to 5 F
0.5 and 1 mg/kg/day: No drug-related findings.
5 and 25 mg/kg/day: Dose-related impairment of motor activity, hyporeactivity, tremors, catalepsy, and abnormal posture. These clinical signs generally were mild at 5 mg/kg/day and severe at 25 mg/kg/day early in the study, but improved with continued dosing at 25 mg/kg/day.
25 mg/kg/day: Minimal decreases in body weight, moderate decreases in food consumption, and sporadic absence of feces in Weeks 1 and 2 and moderate to severe muddy substance in the bile at necropsy.
All drug-related alterations disappeared or improved during the 4-week post-dose period.
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
Monkey/ Cynomolgus
Oral Gavage
39 weeks
0, 25, 50,
4 M
4 F
Due to pronounced clinical signs at 100 mg/kg/day on Day 1, high-dose animals were not treated on Days 2 to 4. Starting on Day 5 through remainder of the study, high-dose animals were treated at 75 mg/kg/day.
25 mg/kg/day: Low incidence of impaired motor activity in 1 male.
25, 50, and 75 mg/kg/day: Dose-related tremors and mild to moderate hypoactivity (transient at 25 mg/kg/day), vomitus (emesis), qualitatively reduced food consumption, low incidences of hunched or unusual posture, and mucus-like and granular (gallsand) materials in the gallbladder.
50 and 75 mg/kg/day: Low incidences of excessive salivation, sternal recumbency, and gallbladder calculi (gallstones); and, microscopically, low incidence of generally minimal liver alterations consistent with hepatolithiasis in the subcapsular parenchyma of the right median lobe proximal to the gallbladder.
75 mg/kg/day: One female euthanatized moribund in Week 3 due to severe clinical toxicity characterized by mild to severe hypoactivity, tremors, excessive salivation, lateral or sternal recumbency, hunched or unusual posture, impaired motor activity, and reduced food consumption (low or none). This female was the only high-dose animal that had not recovered when dosing resumed at 75 mg/kg/day on Day 5. Minimal decreases in body weight in males and low incidence of ataxia in 1 female.
Analyses of gallsand and gallstones indicated that sulfate conjugates of hydroxy metabolites of aripiprazole were the major drug-related constituents; and bile acids, principally taurodeoxycholic acid, were the primary nondrug-related constituents. Analyses of intrahepatic concretions (hepatoliths) demonstrated morphologic features and elemental composition that were similar to gallsand and gallstones.
Species/ Strain
Route of Administration
Duration of Dosing
Dose (mg/kg)
Number / Sex
Noteworthy Findings
Monkey/ Cynomolgus
Oral Gavage
52 weeks
0, 0.5, 5,
25
4 M
4 F
0.5 mg/kg/day: No drug-related changes.
5 and 25 mg/kg/day: Dose-related incidences and/or severity of impaired motor activity, hyporeactivity, tremors, catalepsy, and abnormal posture (crouching, lateral, and/or prone position) that were most evident during Weeks 1 and 2. At 25 mg/kg/day, impaired motor activity was severe in Week 1 and generally mild during the remainder of the study.
Hyporeactivity disappeared by Week 3 and catalepsy and abnormal posture were observed sporadically throughout the dosing period.
25 mg/kg/day: Minimal decreases in body weight and mild to moderate decreases in food consumption during Weeks 1 and 2. At necropsy, slight to generally moderate gallsand in 3 animals and gallstones in 1 animal. In comparison, slight gallsand noted in 2 controls.
In a 28-day oral toxicity study in rats, metabolite 1-(2,3-dichlorophenyl) piperazine (2,3-DCPP) produced CNS-related clinical signs with deaths at the high dose (30 mg/kg/day) but no evidence of target organ toxicity.
Genotoxicity
The mutagenic potential of aripiprazole was tested in the in vitro bacterial reverse-mutation assay, the in vitro bacterial DNA repair assay, the in vitro forward gene mutation assay in mouse lymphoma cells, the in vitro chromosomal aberration assay in Chinese hamster lung (CHL) cells, the in vivo micronucleus assay in mice, and the unscheduled DNA synthesis assay in rats. Aripiprazole was clastogenic in the in vitro chromosomal aberration assay in CHL cells with and without metabolic activation. A positive response was obtained in the in vivo micronucleus assay in mice; however, the response was due to a mechanism considered not relevant to humans.
All 3 metabolites (dehydro-aripiprazole, OPC3373 and 2,3-DCPP) were not mutagenic in bacterial reverse-mutation tests. In an in vitro cytogenetics assay in CHL cells, 2,3-DCPP increased chromosome aberrations in the presence and absence of metabolic activation; however, the increases were considered secondary to excessive cytotoxicity rather than direct DNA reactivity.
Carcinogenicity
Lifetime carcinogenicity studies were conducted in ICR mice and in Sprague-Dawley (SD) and F344 rats. Aripiprazole was administered for 2 years in the diet at doses of 1, 3, 10, and 30 mg/kg/day to ICR mice and 1, 3, and 10 mg/kg/day to F344 rats (0.2 to 5 and 0.3 to 3 times the MRHD based on mg/m2, respectively). In addition, SD rats were dosed orally for 2 years at 10, 20, 40, and 60 mg/kg/day (3 to 19 times the MRHD based on mg/m2). Aripiprazole did not induce tumors in male mice or rats. In female mice, the incidences of pituitary gland adenomas and mammary gland adenocarcinomas and adenoacanthomas were increased at dietary doses of 3 to 30 mg/kg/day (0.1 to 0.9 times human exposure at MRHD based on AUC and 0.5 to 5 times the MRHD based on mg/m2). In female rats, the incidence of mammary gland fibroadenomas was increased at a dietary dose of 10 mg/kg/day (0.1 times human exposure at MRHD based on AUC); and the incidences of adrenocortical carcinomas and combined adrenocortical adenomas/carcinomas were increased at an oral dose of 60 mg/kg/day (10 times human exposure at MRHD based on AUC).
Proliferative changes in the pituitary and mammary gland of rodents have been observed following chronic administration of other antipsychotic agents and are considered prolactin-mediated. Serum prolactin was not measured in the aripiprazole carcinogenicity studies. However, increases in serum prolactin levels were observed in female mice in a 13-week dietary study at the doses associated with mammary gland and pituitary tumors. Serum prolactin was not increased in female rats in 4- and 13-week dietary studies at the dose associated with mammary gland tumors. The relevance for human risk of the findings of prolactin-mediated endocrine tumors in rodents is unknown
Reproductive and Developmental Toxicology
Reproductive Toxicity
In animal studies, aripiprazole demonstrated developmental toxicity, including possible teratogenic effects in rats and rabbits.
Pregnant rats were treated with oral doses of 3, 10, and 30 mg/kg/day (1, 3, and 10 times the maximum recommended human dose [MRHD] on a mg/m2 basis) of aripiprazole during the period of organogenesis. Gestation was slightly prolonged at 30 mg/kg. Treatment caused a slight delay in fetal development, as evidenced by decreased fetal weight (30 mg/kg), undescended testes (30 mg/kg), and delayed skeletal ossification (10 and 30 mg/kg). There were no adverse effects on embryofetal or pup survival. Delivered offspring had decreased bodyweights (10 and 30 mg/kg), and increased incidences of hepatodiaphragmatic nodules and diaphragmatic hernia at 30 mg/kg (the other dose groups were not examined for these findings). A low incidence of diaphragmatic hernia was also seen in the fetuses exposed to 30 mg/kg.
Postnatally, delayed vaginal opening was seen at 10 and 30 mg/kg and impaired reproductive performance (decreased fertility rate, corpora lutea, implants, and live fetuses and increased post-implantation loss, likely mediated through effects on female offspring) was seen at 30 mg/kg. Some maternal toxicity was seen at 30 mg/kg; however, there was no evidence to suggest that these developmental effects were secondary to maternal toxicity.
In pregnant rats receiving aripiprazole injection intravenously (3, 9, and 27 mg/kg/day) during the period of organogenesis, decreased fetal weight and delayed skeletal ossification were seen at the highest dose, which also caused maternal toxicity.
Pregnant rabbits were treated with oral doses of 10, 30, and 100 mg/kg/day (2, 3, and 11 times human exposure at MRHD based on AUC) of aripiprazole during the period of organogenesis. Decreased maternal food consumption and increased abortions were seen at 100 mg/kg. Treatment caused increased fetal mortality (100 mg/kg), decreased fetal weight (30 and 100 mg/kg), increased incidence of a skeletal abnormality (fused sternebrae at 30 and 100 mg/kg), and minor skeletal variations (100 mg/kg).
In pregnant rabbits receiving aripiprazole injection intravenously (3, 10, and 30 mg/kg/day) during the period of organogenesis, the highest dose, which caused pronounced maternal toxicity, resulted in decreased fetal weight, increased fetal abnormalities (primarily skeletal), and decreased fetal skeletal ossification. The fetal no-effect dose was 10 mg/kg, which produced 5 times the human exposure at the MRHD based on AUC.
In a study in which rats were treated with oral doses of 3, 10, and 30 mg/kg/day (1, 3, and 10 times the MRHD on a mg/m2 basis) of aripiprazole perinatally and postnatally (from day 17 of gestation through day 21 postpartum), slight maternal toxicity and slightly prolonged gestation were seen at 30 mg/kg. An increase in stillbirths and decreases in pup weight (persisting into adulthood) and survival were seen at this dose.
In rats receiving aripiprazole injection intravenously (3, 8, and 20 mg/kg/day) from day 6 of gestation through day 20 postpartum, an increase in stillbirths was seen at 8 and 20 mg/kg, and decreases in early postnatal pup weights and survival were seen at 20 mg/kg. These doses produced some maternal toxicity. There were no effects on postnatal behavioral and reproductive development.
Following [14C]-aripiprazole administration to pregnant rats, radioactivity in the fetus was low and only a trace amount was detected in the amniotic fluid. After [14C]-aripiprazole administration to lactating rats, milk vs blood concentration ratios were greater than one for up to 24 hours.
Impairment of Fertility
Female rats were treated with oral doses of 2, 6, and 20 mg/kg/day (0.6, 2, and 6 times the MRHD on a mg/m2 basis) of aripiprazole from 2 weeks prior to mating through day 7 of gestation. Estrus cycle irregularities and increased corpora lutea were seen at all doses, but no impairment of fertility was seen. Increased pre-implantation loss was seen at 6 and 20 mg/kg and decreased fetal weight was seen at 20 mg/kg.
Male rats were treated with oral doses of 20, 40, and 60 mg/kg/day (6, 13, and 19 times the MRHD on a mg/m2 basis) of aripiprazole from 9 weeks prior to mating through mating.
Disturbances in spermatogenesis were seen at 60 mg/kg and prostate atrophy was seen at 40 and 60 mg/kg, but no impairment of fertility was seen.
Juvenile Toxicity
In repeat-dose studies in juvenile rats and dogs, the toxicity profile of aripiprazole was comparable to that observed in adult animals, and there was no evidence of neurotoxicity or adverse effects on development.
Special Toxicology
Adrenocortical Changes in Rats
A series of investigative studies were conducted in rats to determine the mechanism for the aripiprazole-related adrenocortical changes after subchronic and chronic dosing. The data from these studies supported the conclusion that the female rat-specific adrenocortical tumorigenic response at 60 mg/kg/day in the oral carcinogenicity study was secondary to aripiprazole-related adrenocortical cytotoxicity and consequent increased cell proliferation. The female specificity of the adrenocortical tumorigenic response was considered a consequence of the earlier onset and greater severity of the adrenocortical cytotoxic changes. The adrenocortical cytotoxic and tumorigenic effects have no established clinical relevance since they occurred at a dose 10 times human exposure at the MRHD based on AUC.
Retinal Degeneration in Rats
Aripiprazole produced retinal degeneration in albino Sprague-Dawley (SD) rats in a 26-week chronic toxicity study at a dose of 60 mg/kg and in a 2-year carcinogenicity study at doses of 40 and 60 mg/kg. The 40 and 60 mg/kg doses are 7 to 10 times human exposure at the MRHD based on AUC. In a subsequent 18-month investigative study in albino SD and pigmented Long- Evans (LE) rats administered 60 mg/kg/day aripiprazole, pharmacologically mediated hyperactivity occurred in both rat strains early in the study predisposing the animals to increased light exposure. Time-dependent retinal degeneration with electroretinographic and morphologic features consistent with spontaneous light-induced retinal degeneration was observed in albino SD rats, whereas there was no evidence of light-induced retinal injury in pigmented LE rats at any timepoint despite comparable systemic exposures to aripiprazole. This was due to the photoprotective effect of ocular melanin pigment in LE rats. Therefore, the retinal degeneration observed in albino SD rats after chronic dosing at high doses of aripiprazole was considered to be a consequence of drug-related, pharmacologically mediated hyperactivity during the animal room light phase, resulting in increased light exposure rather than a direct drug effect on the retina. Light-induced retinal degeneration in albino SD rats has no established clinical relevance.
Dermal Sensitization and Dermal and Ocular Irritation
Aripiprazole was not a dermal sensitizer in mice and was nonirritating to rabbit skin and eye.
Phototoxicity
Aripiprazole was nonphototoxic in Balb/c 3T3 mouse fibroblast cultures.
Antigenicity
Aripiprazole produced no evidence of active systemic anaphylaxis or passive cutaneous reactions in guinea pigs.
Immunotoxicity
Aripiprazole did not adversely affect the T-cell-dependent humoral immune response to sheep red blood cells in rats.
Dependence
In a battery of studies conducted to evaluate physical dependence and abuse potential, aripiprazole demonstrated no abuse liability in rats; mild, transient physical dependence in monkeys (rebound arousal) considered to be of little clinical significance; and no positive reinforcing effects in monkeys. Overall, the results support that aripiprazole has no abuse liability.
17. Supporting Product Monographs
- 1. PrABILIFY® (aripiprazole tablets, 2 mg, 5 mg, 10 mg, 15 mg, 20 mg and 30 mg), control number 242200, Product Monograph, Otsuka Pharmaceuticals Co., Ltd. (February 11, 2021)