


Product Monograph - Abilify Maintena
Recent Major Label Changes
| 1 Indications | 2025-08 |
|---|---|
| 2 Contraindications | 2025-01 |
| 3 Serious Warnings and Precautions Box | 2025-08 |
| 4.1 Dosing Considerations | 2025-08 |
| 4.2 Recommended Dose and Dosage Adjustment | 2025-08 |
| 4.3 Reconstitution | 2025-08 |
| 4.4 Administration | 2025-08 |
| 7 Warnings and Precautions | 2025-08 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................. 2
Table of Contents ................................................................................................................. 2
Part 1: Healthcare Professional Information.......................................................................... 4
- 1.
Indications..................................................................................................................... 4
1.1. Pediatrics .................................................................................................................... 4
1.2. Geriatrics .................................................................................................................... 4
- 2. Contraindications .......................................................................................................... 4
- 3. Serious Warnings and Precautions Box ........................................................................... 4
- 4.
Dosage and Administration ............................................................................................ 4
4.1. Dosing Considerations ............................................................................................... 4
4.2. Recommended Dose and Dosage Adjustment .......................................................... 5
4.3. Reconstitution ............................................................................................................ 7
4.4. Administration ......................................................................................................... 18
4.5. Missed Dose ............................................................................................................. 19
- 5. Overdose ..................................................................................................................... 19
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................ 21
- 7.
Warnings and Precautions ........................................................................................... 21
General ................................................................................................................................. 21
Carcinogenesis and Genotoxicity ......................................................................................... 22
Cardiovascular ...................................................................................................................... 22
Driving and Operating Machinery ........................................................................................ 23
Endocrine and Metabolism .................................................................................................. 23
Genitourinary ....................................................................................................................... 24
Hematologic ......................................................................................................................... 24
Monitoring and Laboratory Tests ......................................................................................... 24
Neurologic ............................................................................................................................ 25
Psychiatric ............................................................................................................................. 26
Skin .................................................................................................................................. 27
7.1. Special Populations .................................................................................................. 27
7.1.1. Pregnancy ......................................................................................................... 27
7.1.2. Breastfeeding ................................................................................................... 27
7.1.3. Pediatrics .......................................................................................................... 27
7.1.4. Geriatrics .......................................................................................................... 28
- 8.
Adverse Reactions ....................................................................................................... 29
8.1. Adverse Reaction Overview ..................................................................................... 29
8.2. Clinical Trial Adverse Reactions ............................................................................... 29
8.3. Less Common Clinical Trial Adverse Reactions ........................................................ 38
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ................................................................................................................. 40
8.5. Post-Market Adverse Reactions ............................................................................... 41
- 9.
Drug Interactions ......................................................................................................... 42
9.2. Drug Interactions Overview ..................................................................................... 42
9.3. Drug-Behaviour Interactions .................................................................................... 42
9.4. Drug-Drug Interactions ............................................................................................ 43
9.5. Drug-Food Interactions ............................................................................................ 44
9.6. Drug-Herb Interactions ............................................................................................ 44
9.7. Drug-Laboratory Test Interactions........................................................................... 44
- 10.
Clinical Pharmacology .................................................................................................. 44
10.1. Mechanism of Action ............................................................................................... 44
10.2. Pharmacodynamics .................................................................................................. 45
10.3. Pharmacokinetics ..................................................................................................... 45
- 11. Storage, Stability, and Disposal .................................................................................... 47
Part 2: Scientific Information .............................................................................................. 48
- 13. Pharmaceutical Information ........................................................................................ 48
- 14.
Clinical Trials ............................................................................................................... 48
14.1. Clinical Trials by Indication ...................................................................................... 48
Schizophrenia ....................................................................................................................... 48
Bipolar I Disorder .................................................................................................................. 55
- 16. Non-Clinical Toxicology ................................................................................................ 58
Patient Medication Information ......................................................................................... 63
Part 1: Healthcare Professional Information
1. Indications
ABILIFY MAINTENA (aripiprazole for prolonged release injectable suspension) is a one-month injection indicated for:
- treatment of schizophrenia in adult patients.
- maintenance monotherapy treatment of bipolar I disorder in adult patients.
Efficacy of ABILIFY MAINTENA was established in both acute and maintenance phases of schizophrenia in controlled clinical trials. In patients in the acute phase of schizophrenia, ABILIFY MAINTENA was superior to placebo in improving both positive and negative symptoms of schizophrenia. ABILIFY MAINTENA was found to prevent relapse for up to 38 weeks after stabilization with oral aripiprazole (see 14.1 Clinical Trials by Indication, Schizophrenia).
In a controlled clinical trial in adult patients with bipolar I disorder, ABILIFY MAINTENA significantly reduced the risk of recurrence of any mood episode over 52 weeks compared with placebo (see 14.1 Clinical Trials by Indication, Bipolar I Disorder).
1.1. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada for patients <18 years of age; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2. Geriatrics
Geriatrics (> 65 years of age): ABILIFY MAINTENA is not indicated in elderly patients with dementia (see 3 Serious Warnings and Precautions Box and 7.1.4 Geriatrics). The safety and efficacy of ABILIFY MAINTENA in patients 65 years of age or older have not been established. Caution should be used when treating geriatric patients (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
2. Contraindications
ABILIFY MAINTENA is contraindicated in patients who are hypersensitive to aripiprazole or to any ingredient in the formulation, including any non-medicinal ingredient, or to a component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
Increased Mortality in Elderly Patients with Dementia
Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to those treated with placebo (see 7.1.4 Geriatrics). ABILIFY MAINTENA is not approved for use in elderly patients with dementia.
4. Dosage and Administration
4.1. Dosing Considerations
For patients who have never taken aripiprazole, including those who are switching from other oral antipsychotics, establish tolerability with oral aripiprazole prior to initiating treatment with ABILIFY MAINTENA.
ABILIFY MAINTENA is only to be administered by intramuscular injection in the gluteal or deltoid muscle by a healthcare professional.
4.2. Recommended Dose and Dosage Adjustment
Tolerability with oral aripiprazole must be established prior to initiating treatment with ABILIFY MAINTENA (see 4.1 Dosing Considerations). Titration of the dose of ABILIFY MAINTENA is not required.
Initiating ABILIFY MAINTENA
Based on clinical study data, the treatment can be initiated using one injection start:
- One injection start from oral aripiprazole or another oral antipsychotic: On the day of treatment initiation, administer one injection of 400 mg ABILIFY MAINTENA along with 10 mg to 20 mg oral aripiprazole or current oral antipsychotic for 14 consecutive days to maintain therapeutic antipsychotic concentrations during initiation of therapy. Administer the next monthly 400 mg single injection no sooner than 26 days after the previous injection.
Based on modelling and simulation study data, the treatment can also be initiated using a two injection start:
Two injection start from oral aripiprazole or another oral antipsychotic: Patients must discontinue their current oral antipsychotic upon initiation of ABILIFY MAINTENA. On the day of treatment initiation, administer two separate injections of 400 mg ABILIFY MAINTENA at separate injection sites (see 4.4 Administration) along with one 20 mg dose of oral aripiprazole.
Administer the next monthly 400 mg single injection no sooner than 26 days after the previous injection.
Maintenance dose
The recommended maintenance dose of ABILIFY MAINTENA is 400 mg. ABILIFY MAINTENA should be administered by a healthcare professional once monthly as a single injection no sooner than 26 days after the previous injection. If there are adverse reactions with the 400 mg dosage, reduction of the dose to 300 mg once monthly should be considered. If ABILIFY MAINTENA is discontinued, its prolonged release characteristics must be considered.
Dosage Adjustments Based on Cytochrome P450 Activities
Dosage reductions are recommended in patients who are known CYP2D6 poor metabolizers and in patients taking concomitant strong CYP3A4 inhibitors or strong CYP2D6 inhibitors. Refer to Table 1 (see 9.4 Drug-Drug Interactions).
Table 1: Dose Adjustments of ABILIFY MAINTENA in patients who are known CYP2D6 poor metabolizers and patients taking concomitant strong CYP2D6 inhibitors, strong CYP3A4 inhibitors, and/or CYP3A4 inducers*
| Adjusted Dose | ||||
|---|---|---|---|---|
| Known CYP2D6 Poor Metabolizers | ||||
| Known CYP2D6 Poor Metabolizers |
Maintenance dose: 300 mg | |||
| Known CYP2D6 Poor Metabolizers taking strong concomitant CYP3A4 inhibitors |
| |||
| Patients Taking 400 mg of ABILIFY MAINTENA as maintenance dose, with a concomitant drug | ||||
| Strong CYP2D6 or Strong CYP3A4 inhibitors | 300 mg | |||
| Strong CYP2D6 and Strong CYP3A4 inhibitors | 200 mg | |||
| CYP3A4 inducers | Avoid use | |||
| Patients Taking 300 mg of ABILIFY MAINTENA as maintenance dose, with a concomitant drug | ||||
| Strong CYP2D6 or Strong CYP3A4 inhibitors | 200 mg | |||
| Strong CYP2D6 and Strong CYP3A4 inhibitors | 160 mg | |||
| CYP3A4 inducers | Avoid use | |||
* The same recommendations may not be applicable to all durations and scenarios of concomitant use.
Special Populations
Elderly population
The safety and efficacy of ABILIFY MAINTENA in patients 65 years of age or older have not been established. No dosage adjustment of ABILIFY MAINTENA is recommended for elderly patients; however, owing to the greater sensitivity of this population, a lower starting dose should be considered when clinical factors warrant.
ABILIFY MAINTENA is not indicated in elderly patients with dementia (see 3 Serious Warnings and Precautions Box; 7.1.4 Geriatrics).
Renal impairment
No dosage adjustment of ABILIFY MAINTENA is required for patients with renal impairment.
Hepatic impairment
No dosage adjustment of ABILIFY MAINTENA is required for patients with mild or moderate hepatic impairment. There are insufficient data to establish dosing recommendations for patients with severe hepatic impairment. In these patients dosing should be managed cautiously; use of oral aripiprazole should be considered.
Other special populations
No dosage adjustment of ABILIFY MAINTENA is recommended based on gender, race, or smoking status.
4.3. Reconstitution
Vial
Step 1: Preparation Prior to Reconstitution of the Lyophilized ABILIFY MAINTENA Powder.
- (a)
Lay out and confirm that components listed below are provided:
- • Vial of ABILIFY MAINTENA (aripiprazole for prolonged release injectable suspension)
- • 2.0-mL vial of solvent (sterile water for injection)
- • One 3-mL Luer lock syringe with pre-attached 21g x 1 ½-inch (38 mm) hypodermic needle with needle protection device
- • One 3-mL disposable syringe with Luer lock tip
- • One vial adapter
- • One 22 gauge, 1 ½-inch (38 mm) hypodermic needle with needle protection device
- • One 21 gauge, 2-inch (51 mm) hypodermic needle with needle protection device
- • One 23 gauge, 1-inch (25 mm) hypodermic needle with needle protection device
- (b) ABILIFY MAINTENA should be suspended using the Sterile Water for Injection supplied in the carton.
- (c) The Sterile Water for Injection and ABILIFY MAINTENA vials are for single-use only.
- (d) Use appropriate aseptic techniques throughout reconstitution and reconstitute at room temperature.
- (e) Select the amount of Sterile Water for Injection needed for reconstitution.
| 400 mg Vial | 300 mg Vial | ||
|---|---|---|---|
| Dose | Sterile Water for Injection | Dose | Sterile Water for Injection |
| 400 mg | 1.9 mL | 300 mg | 1.5 mL |
It is important to note that there is more Sterile Water for Injection in the vial than is needed to reconstitute ABILIFY MAINTENA (aripiprazole for prolonged release injectable suspension).
Step 2: Reconstitution of the Lyophilized Powder
- (a) Remove the cap of the vial of Sterile Water for Injection and remove the cap of the vial containing ABILIFY MAINTENA lyophilized powder and wipe the tops with a sterile alcohol swab.
- (b) Using the 3 mL syringe with pre-attached hypodermic safety needle, withdraw the pre-determined Sterile Water for Injection volume from the vial of Sterile Water for Injection into the syringe (Figure 1). A small amount of residual Sterile Water for Injection will remain in the vial following withdrawal.
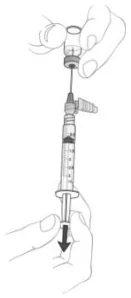
Figure 1
- (c) Slowly inject the Sterile Water for Injection into the vial containing the ABILIFY MAINTENA lyophilized powder (Figure 2).
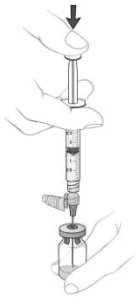
Figure 2
- (d) Withdraw air to equalize the pressure in the vial by pulling back slightly on the plunger. Subsequently, remove the needle from the vial. Engage the needle safety device by using the one-handed technique (Figure 3). Gently press the sheath against a flat surface until the needle is firmly engaged in the needle protection sheath. Visually confirm that the needle is fully engaged into the needle protection sheath, and discard.
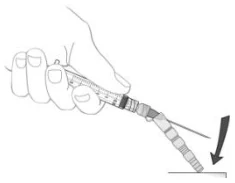
Figure 3
- (e) Shake the vial vigorously for 30 seconds until the suspension appears uniform (Figure 4).
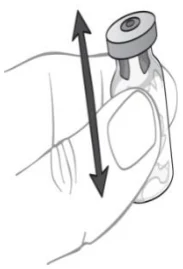
Figure 4
- (f) Visually inspect the reconstituted suspension for particulate matter and discolouration prior to administration. The reconstituted ABILIFY MAINTENA is a uniform, homogeneous suspension that is opaque and milky-white in colour.
- (g) If the injection is not performed immediately after reconstitution, keep the vial below 25°C for up to four hours and shake the vial vigorously for at least 60 seconds to re-suspend prior to injection.
- (h) Do not store the reconstituted suspension in the syringe.
Step 3: Preparation Prior to Injection
- (a) Use appropriate aseptic techniques throughout injection of the reconstituted ABILIFY MAINTENA suspension.
- (b) Remove the cover from the vial adapter package (Figure 5). Do not remove the vial adapter from the package.
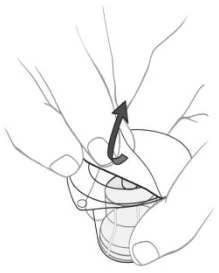
Figure 5
- (c) Using the vial adapter package to handle the vial adapter, attach the prepackaged Luer lock syringe to the vial adapter (Figure 6).
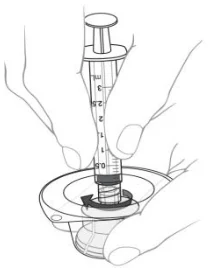
Figure 6
- (d) Use the Luer lock syringe to remove the vial adapter from the package and discard the vial adapter package (Figure 7). Do not touch the spike tip of the adapter at any time.
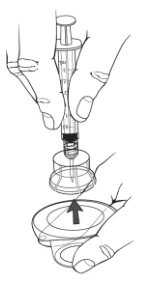
Figure 7
- (e)
Determine the recommended volume for injection.
ABILIFY MAINTENA Reconstituted Suspension Volume to Inject
| 400 mg Vial | 300 mg Vial | ||
|---|---|---|---|
| Dose | Volume to Inject | Dose | Volume to Inject |
| 400 mg | 2 mL | --- | --- |
| 300 mg | 1.5 mL | 300 mg | 1.5 mL |
| 200 mg | 1 mL | 200 mg | 1 mL |
| 160 mg | 0.8 mL | 160 mg | 0.8 mL |
- (f) Wipe the top of the vial of the reconstituted ABILIFY MAINTENA suspension with a sterile alcohol swab.
- (g) Place and hold the vial of the reconstituted ABILIFY MAINTENA suspension on a hard surface. Attach the adapter-syringe assembly to the vial by holding the outside of the adapter and pushing the adapter’s spike firmly through the rubber stopper, until the adapter snaps in place (Figure 8).
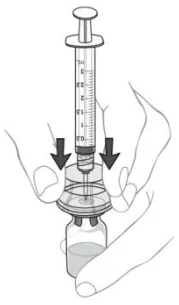
Figure 8
- (h) Slowly withdraw the recommended volume from the vial into the Luer lock syringe to allow for injection (Figure 9). A small amount of excess product will remain in the vial. Once ABILIFY MAINTENA is in the syringe, it must be used immediately.
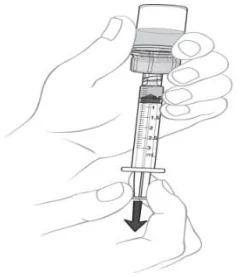
Figure 9
Step 4: Injection Procedure
- (a) Detach the Luer lock syringe containing the recommended volume of reconstituted ABILIFY MAINTENA suspension from the vial.
- (b) Select the appropriate hypodermic needle and attach the needle to the Luer lock syringe containing the suspension for injection. While holding the needle cap, ensure the needle is firmly seated on the safety device with a push and clockwise twist until snugly fitted and then pull the needle cap straight away from the needle (Figure 10).
For deltoid administration:
For gluteal administration:
| Body Type | Needle Size | Needle Hub Colour |
|---|---|---|
 Person living without obesity | 1-inch (25 mm), 23 gauge | blue |
 Person living with obesity | 1 ½-inch (38 mm), 22 gauge |
| Body Type | Needle Size | Needle Hub Colour |
|---|---|---|
Person living without obesity | 1 ½-inch (38 mm), 22 gauge | |
Person living with obesity | 2-inch (51 mm), 21 gauge | green |
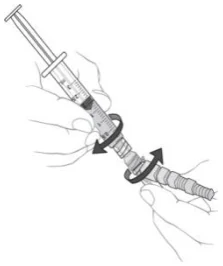
Figure 10
- (c) Slowly inject the recommended volume as a single intramuscular injection into the deltoid or gluteal muscle. Do not massage the injection site.
Do not administer intravenously or subcutaneously or by any other route.
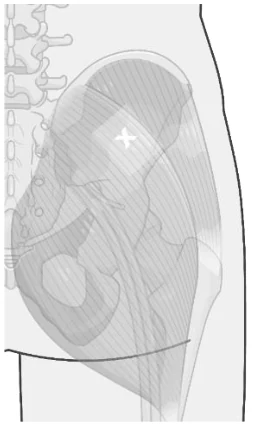
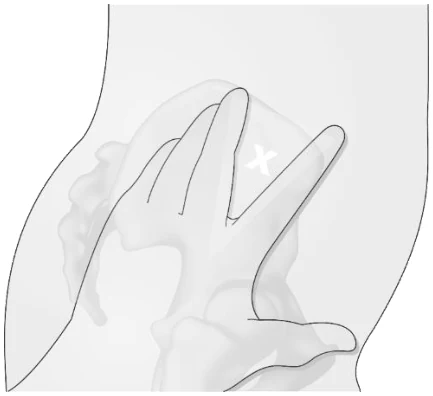
Ventrogluteal site
Dorsogluteal site
Figure 11
Step 5: Procedures After Injection
- (a) Engage the needle safety device as described in Step 2 (d). Dispose of the vials, adapter, needles, and syringe appropriately after injection. The Sterile Water for Injection and ABILIFY MAINTENA vials are for single-use only.
- (b) Rotate sites of injections between the two deltoid or gluteal muscles. If initiating with the two injection start, inject in two different muscles (right or left deltoid muscle or right or left gluteal muscle). DO NOT inject both injections concomitantly into the same deltoid or gluteal muscle.
Dual Chamber Syringe (currently not available in Canada)
Step 1: Preparation Prior to Reconstitution of the Lyophilized ABILIFY MAINTENA Powder
Lay out and confirm that components listed below are provided in the kit:
One ABILIFY MAINTENA (aripiprazole for prolonged release injectable suspension) pre-filled
- dual chamber syringe (400 mg or 300 mg as appropriate) containing lyophilized powder and Sterile Water for Injection
- One 22 gauge, 1½-inch (38 mm) hypodermic needle with needle protection device
- One 21 gauge, 2-inch (51 mm) hypodermic needle with needle protection device
- One 23 gauge, 1-inch (25 mm) hypodermic needle with needle protection device
Step 2: Reconstitution of the Lyophilized Powder in Pre-filled Dual Chamber Syringe Reconstitute at room temperature.
- (a) Push plunger rod slightly to engage threads. And then, rotate plunger rod until the rod stops rotating to release diluent. After plunger rod is at complete stop, middle stopper will be at the indicator line (Figure 12).
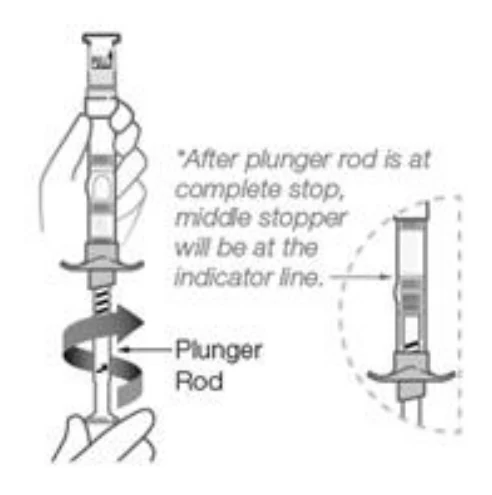
Figure 12
- (b) Vertically shake the syringe vigorously for 20 seconds until drug is uniformly milky-white (Figure 13).
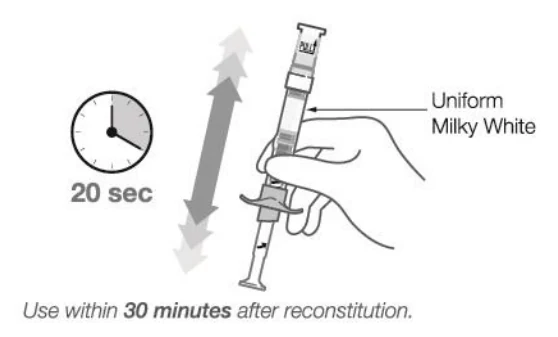
Figure 13
- (c) Visually inspect the syringe for particulate matter and discolouration prior to administration. The reconstituted ABILIFY MAINTENA suspension should appear to be a uniform, homogeneous suspension that is opaque and milky-white in colour.
Step 3: Injection Procedure
Use appropriate aseptic techniques throughout injection procedure. Do not administer intravenously or subcutaneously.
- (a) Twist and pull off Over-cap and Tip-cap (Figure 14).
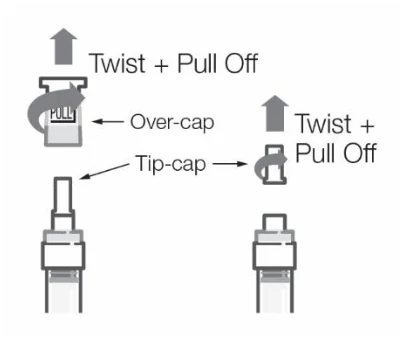
Figure 14
- (b) Select appropriate needle. Needle selection is determined by patient body type and location of administration.
For deltoid administration:
| Body Type | Needle Size | Needle Hub Colour |
|---|---|---|
Person living without obesity | 1-inch (25 mm), 23 gauge | blue |
Person living with obesity | 1 ½-inch (38 mm), 22 gauge |
For gluteal administration:
- (c) While holding the needle cap, ensure the needle is firmly seated on the safety device with a push. Twist clockwise until SNUGLY fitted (Figure 15).
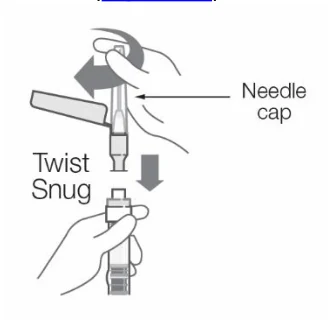
Figure 15
- (d) Then PULL needle-cap straight up (Figure 16).
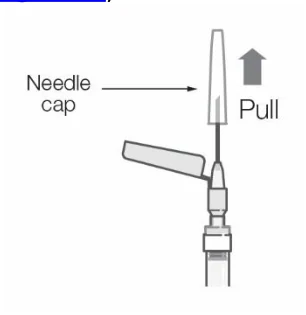
Figure 16
| Body Type | Needle Size | Needle Hub Colour |
|---|---|---|
Person living without obesity | 1 ½-inch (38 mm), 22 gauge | |
Person living with obesity | 2-inch (51 mm), 21 gauge | green |
- (e) Hold syringe UPRIGHT and ADVANCE PLUNGER ROD SLOWLY TO EXPEL THE AIR. Expel air until suspension fills needle base. If it’s not possible to advance plunger rod to expel the air, check that plunder rod is rotated to a complete stop (Figure 17).
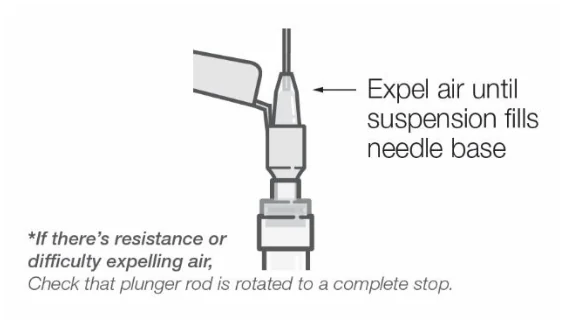
Figure 17
- (f) Inject slowly into the deltoid or gluteal muscle. Do not massage the injection site. Do not administer intravenously or subcutaneously.
Ventrogluteal site
Dorsogluteal site
Figure 18
Step 4: Disposal Procedure
- (a) Engage the needle safety device as described in Step 2 (d) of Reconstitution of Lyophilized Powder in Vial and safely discard all kit components (Figure 19). ABILIFY MAINTENA pre-filled dual chamber syringe is for single-use only.
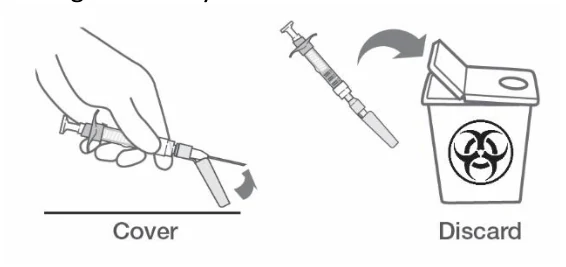
Figure 19
(b) Rotate sites of injections between the two deltoid or gluteal muscles.
4.4. Administration
ABILIFY MAINTENA comes in two types of kits. See 4.3 Reconstitution for instructions for reconstitution/injection/disposal procedures for 1) single-use vials available in 300 mg or 400 mg strengths and, 2) Pre-filled Dual Chamber Syringe presented in 300 mg or 400 mg strength syringes.
ABILIFY MAINTENA is for deep intramuscular deltoid or gluteal injection: do not administer intravenously or subcutaneously.
Inject immediately after reconstitution. ABILIFY MAINTENA should be administered by a healthcare professional once monthly as a single injection.
4.5. Missed Dose
Table 2: Management of Missed Doses
| Missed doses | |
|---|---|
| Timing of Missed Dose | Action |
| If 2nd or 3rd dose is missed and time since last injection is: | |
| >4 weeks and <5 weeks | Administer the injection as soon as possible and then resume monthly injection schedule. |
| >5 weeks | Either administer one injection of 400 mg ABILIFY MAINTENA along with 10 mg to 20 mg oral aripiprazole for 14 consecutive days. The next monthly 400 mg single injection should not be sooner than 26 days after the previous injection. OR Administer two separate injections of 400 mg ABILIFY MAINTENA at separate injection sites along with one 20 mg dose of oral aripiprazole. The next monthly 400 mg single injection should not be sooner than 26 days after the previous injections. |
| If 4th or subsequent doses are missed and time since last injection is: | |
| >4 weeks and <6 weeks | Administer the injection as soon as possible and then resume monthly injection schedule. |
| >6 weeks | Either administer one injection of 400 mg ABILIFY MAINTENA along with 10 mg to 20 mg oral aripiprazole for 14 consecutive days. The next monthly 400 mg single injection should not be sooner than 26 days after the previous injection. OR Administer two separate injections of 400 mg ABILIFY MAINTENA at separate injection sites along with one 20 mg dose of oral aripiprazole. The next monthly 400 mg single injection should not be sooner than 26 days after the previous injections. |
5. Overdose
No cases of overdose were reported in clinical studies with aripiprazole injection. Because ABILIFY MAINTENA is to be administered by healthcare professionals, the potential for overdosage by patients is low.
While overdose is less likely with parenteral than oral medicinal products, reference information for oral aripiprazole overdose is presented below.
Symptoms
In post-marketing experience with oral aripiprazole, there is a single case of death that was possibly associated with accidental or intentional acute overdosage of aripiprazole alone. The patient ingested 900 mg of aripiprazole, was hospitalized in the intensive care unit for 10 to 14 days and died. The patient’s medical history included excessive alcohol use, although it is unclear whether alcohol was present at the time of overdosage. In the patient taking the largest confirmed amount of aripiprazole, 1680 mg, the only symptoms reported were vomiting, fatigue, and dizziness. Other potentially medically important signs and symptoms that have been observed during overdose included blood pressure increased, lethargy, somnolence, tachycardia, nausea, vomiting and diarrhea. In the patients who were evaluated in hospital settings, there were no reported observations indicating clinically important adverse change in vital signs, laboratory assessments, or electrocardiogram.
Common adverse reactions (reported in at least 5% of all overdose cases) reported with oral aripiprazole overdosage (alone or in combination with other substances) include vomiting, somnolence, and tremor. Other clinically important signs and symptoms observed in one or more patients with aripiprazole overdoses (alone or with other substances) include acidosis, aggression, aspartate aminotransferase increased, atrial fibrillation, bradycardia, coma, confusional state, convulsion, blood creatine phosphokinase increased, depressed level of consciousness, hypertension, hypokalemia, hypotension, lethargy, loss of consciousness, QRS complex prolonged, QT prolonged, pneumonia aspiration, respiratory arrest, status epilepticus, and tachycardia.
Management
Management of overdose should concentrate on supportive therapy, maintaining an adequate airway, oxygenation and ventilation, and management of symptoms. The possibility of multiple medicinal product involvement should be considered. Therefore, cardiovascular monitoring should be started immediately and should include continuous electrocardiographic monitoring to detect possible arrhythmias. Following any confirmed or suspected overdose with aripiprazole, close medical supervision and monitoring should continue until the patient recovers. There is no specific antidote to aripiprazole.
Consider the prolonged release characteristics of ABILIFY MAINTENA and the half-life of aripiprazole when assessing treatment needs and recovery.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 3: Dosage Forms, Strengths, Composition and Packaging
*currently not available in Canada
Vial:
ABILIFY MAINTENA is available in two dosage strengths, 300 mg and 400 mg and is provided as a lyophilized powder for reconstitution. One carton contains one vial of powder, one vial of solvent (sterile water for injection), one 3 mL sterile syringe with a 21 gauge needle for reconstitution, one sterile syringe without needle, one 1 ½-inch (38 mm) 22 gauge sterile safety needle, one 2-inch (51 mm) 21 gauge sterile safety needle, one 1-inch (25 mm) 23 gauge hypodermic safety needle with needle protection device and one vial adapter.
ABILIFY MAINTENA is presented in a Type-I glass vial stoppered with a Teflon laminated rubber stopper and sealed with a flip-off aluminium cap.
Dual chamber syringe (currently not available in Canada):
ABILIFY MAINTENA pre-filled dual chamber syringe in single-use syringes is presented as 300 mg or 400 mg strength syringes. The pre-filled dual chamber syringe consists of a front chamber that contains the lyophilized powder of aripiprazole monohydrate and a rear chamber that contains sterile water for injection. One carton contains one single-use pre-filled dual chamber syringe containing powder and solvent, one 1 ½-inch (38 mm) 22 gauge sterile safety needle, one 2-inch (51 mm) 21 gauge sterile safety needle and one 1-inch (25 mm) 23 gauge hypodermic safety needle.
7. Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information.
General
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing ABILIFY MAINTENA for patients who will be experiencing conditions which may contribute to an elevation in core body temperature (e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
ABILIFY MAINTENA Intra-muscular injection (deltoid or gluteal) | Powder for prolonged release injectable suspension:
| carboxymethyl cellulose sodium mannitol sodium hydroxide sodium phosphate monobasic monohydrate |
anticholinergic activity, or being subject to dehydration).
Carcinogenesis and Genotoxicity
For animal data, see 16 Non-Clinical Toxicology.
Cardiovascular
Orthostatic Hypotension
Aripiprazole may be associated with orthostatic hypotension, perhaps due to its α1-adrenergic receptor antagonism. Aripiprazole may induce orthostatic hypotension, tachycardia, dizziness, and sometimes syncope, especially at the initiation of treatment. In the placebo-controlled trial in acute schizophrenia, presyncope occurred in 1/167 (0.6%) of patients treated with ABILIFY MAINTENA, while syncope and orthostatic hypotension each occurred in 1/172, (0.6%) of patients treated with placebo. There were no significant orthostatic changes in blood pressure for the ABILIFY MAINTENA-treated patients or placebo-treated patients (defined as a decrease in systolic blood pressure ≥20 mmHg accompanied by an increase in heart rate ≥25 when comparing standing to supine values). In the double-blind controlled phase of the schizophrenia maintenance clinical trials using ABILIFY MAINTENA, orthostatic related events were reported in 2/534 (0.4%) patients. Orthostasis occurred in 4/576 (0.7%) patients treated with ABILIFY MAINTENA during the stabilization phase, including abnormal orthostatic blood pressure (1/576, 0.2%), postural dizziness (1/576, 0.2%), presyncope (1/576, 0.2%) and orthostatic hypotension (1/576, 0.2%). In the stabilization phase, the incidence of significant orthostatic change in blood pressure was 0.2% (1/575). During the stabilization phase of the maintenance trial in adult patients with bipolar I disorder, syncope was the only orthostatic related adverse event reported in 0.2% of patients treated with ABILIFY MAINTENA. Incidence of potential clinically relevant orthostatic hypotension reported during the ABILIFY MAINTENA stabilization phase in bipolar I disorder was 0.2% (1/421) and during the double-blind, placebo-controlled phase, there were no differences reported in either treatment group. The incidence of orthostatic hypotension-associated events from short-term, placebo-controlled trials of adult patients on oral aripiprazole (n=2643) included (aripiprazole incidence, placebo incidence): orthostatic hypotension (1.0%, 0.3%), postural dizziness (0.5%, 0.3%), and syncope (0.5%, 0.3%). Aripiprazole should be used with caution in patients with known cardiovascular disease (e.g. history of myocardial infarction or ischemic heart disease, heart failure or conduction abnormalities), cerebrovascular disease, or conditions which would predispose patients to hypotension (e.g., dehydration, hypovolemia, and treatment with antihypertensive medications). Patients with a history of clinically significant cardiovascular disorders were excluded from clinical trials. Monitoring of orthostatic vital signs should be considered in patients who are vulnerable to hypotension. QT Interval In clinical trials with ABILIFY MAINTENA, the incidence of QT prolongation was comparable to placebo. In post-marketing experience, QT prolongation has been reported very rarely with aripiprazole treatment. As with other antipsychotics, aripiprazole should be used with caution in patients with conditions such as congenital long QT syndrome and acquired long QT syndrome (e.g., due to concomitant use of a drug that prolongs the QT); a family history of QT prolongation; or other clinical conditions that predispose to arrhythmias (e.g., hypokalemia or hypomagnesemia or hypocalcemia) (see 8.2 Clinical Trial Adverse Reactions).
Driving and Operating Machinery
Antipsychotics, including aripiprazole, have the potential to impair judgment, thinking, or motor skills. While taking ABILIFY MAINTENA, patients should be cautioned to not drive, operate dangerous machinery or engage in activities that require alertness or physical coordination if they are experiencing any of these effects.
Endocrine and Metabolism
Hyperglycemia and Diabetes Mellitus
Diabetic ketoacidosis has occurred in patients treated with antipsychotics with no reported history of hyperglycemia. As with some other antipsychotics, exacerbation of pre-existing diabetes and hyperglycemia have been reported rarely and diabetic ketoacidosis and diabetic coma including some fatal cases, have been reported very rarely during the use of oral aripiprazole. In schizophrenia clinical trials with ABILIFY MAINTENA there have been few reports of hyperglycemia and diabetes, the incidence was 0.6% and 1.1% respectively in the maintenance trials and 0% and 0.6% in the acute trial. In the bipolar I disorder clinical trial, the incidence of hyperglycemia and diabetes were 0.8% and 0% respectively. Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies which did not include oral aripiprazole suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with the atypical antipsychotics. Because aripiprazole was not marketed at the time these studies were performed, it is not known if aripiprazole is associated with this increased risk. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available. Patients should have baseline and periodic monitoring of blood glucose and body weight. Any patient treated with atypical antipsychotics should also be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Dyslipidemia
Undesirable alterations in lipids have been observed in patients treated with atypical antipsychotics (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data).
Weight Gain
Antipsychotic drugs have been associated with metabolic changes, including weight gain. Clinical monitoring of weight is recommended, (see 8.2 Clinical Trial Adverse Reactions Weight).
Genitourinary
Priapism
Although no cases of priapism were reported in clinical trials with ABILIFY MAINTENA, rare cases of priapism have been reported with antipsychotic use including oral aripiprazole. As with other psychotropic drugs, this adverse reaction did not appear to be dose-dependent and did not correlate with the duration of treatment.
Hematologic
In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including aripiprazole. Agranulocytosis has also been reported. Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug-induced leukopenia/neutropenia. Patients with a history of a clinically significant low WBC or drug-induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and discontinuation of ABILIFY MAINTENA should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors. Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Discontinue ABILIFY MAINTENA in patients with severe neutropenia (absolute neutrophil count <1x10⁹/L) and follow their WBC counts until recovery, (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data).
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs, including oral aripiprazole, in case reports and/or observational studies. When prescribing aripiprazole all potential risk factors for VTE should be identified and preventative measures undertaken.
Monitoring and Laboratory Tests
Monitoring for orthostatic vital signs is recommended in patients who may be vulnerable to hypotension (see 7 Cardiovascular).
Baseline measurements and periodic monitoring of blood glucose and body weight is recommended for all patients (see 7 Endocrine and Metabolism).
Frequent monitoring of CBC during the first few months of treatment is recommended in patients with a history of a clinically significant low WBC or drug-induced leukopenia/neutropenia. Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur (see 7 Hematologic).
Neurologic
Neuroleptic Malignant Syndrome (NMS)
Neuroleptic malignant syndrome is a potentially fatal symptom complex that has been reported in association with antipsychotic drugs, including oral aripiprazole. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase (CPK), myoglobinuria (rhabdomyolysis), and acute renal failure. In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.), and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology. The management of NMS should include 1) immediate discontinuation of all antipsychotic drugs including ABILIFY MAINTENA and other drugs not essential to therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment for uncomplicated NMS. If a patient requires antipsychotic drug treatment after recovery from NMS, the potential reintroduction of therapy should be very carefully considered. The patient should be carefully monitored, since recurrence of NMS has been reported.
Falls
Antipsychotics, including aripiprazole, may cause somnolence, postural hypotension, motor and sensory instability, which may lead to falls and, consequently, fractures or other injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, complete fall risk assessments when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Tardive Dyskinesia
A syndrome of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome is highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown. The risk of developing tardive dyskinesia and the likelihood that it will become irreversible increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increases. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses. There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and, thereby, may possibly mask the underlying process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown. Given these considerations, ABILIFY MAINTENA should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that (1) is known to respond to antipsychotic drugs and (2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In such patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically. If signs and symptoms of tardive dyskinesia appear in a patient on ABILIFY MAINTENA, drug discontinuation should be considered. However, some patients may require treatment with ABILIFY MAINTENA despite the presence of the syndrome.
Extrapyramidal Symptoms
See 8.2 Clinical Trial Adverse Reactions - Extrapyramidal Symptoms.
Seizure/Convulsion
As with other antipsychotic drugs, ABILIFY MAINTENA should be used cautiously in patients with a history of seizures or with conditions that lower the seizure threshold. Conditions that lower the seizure threshold may be more prevalent in a population of 65 years or older.
Psychiatric
Suicide
The possibility of a suicide attempt is inherent in psychotic illnesses and close supervision and appropriate clinical management of high-risk patients should accompany drug therapy. As ABILIFY MAINTENA is to be administered by a healthcare professional, suicide due to an overdose is considered unlikely (see 5 Overdose).
Pathological Gambling and Other Impulse-Control Disorders
Post-marketing reports of pathological gambling have been reported in patients treated with aripiprazole. These reports suggest that patients can experience increased urges, particularly for gambling, and the inability to control these urges while taking aripiprazole. With regards to pathological gambling, patients with a prior history of gambling disorder may be at increased risk and should be monitored carefully. Other urges, reported very rarely, include: increased sexual urges, compulsive spending, binge or compulsive eating, and other impulsive and compulsive behaviours. Because patients may not recognize these behaviours as abnormal, it is important for prescribers to ask patients or their caregivers specifically about the development of new or increased gambling urges, sexual urges, compulsive spending, binge or compulsive eating, or other urges while being treated with aripiprazole. It should be noted that impulse-control symptoms can be associated with the underlying disorder; however, in some cases, although not all, urges were reported to have stopped when the dose was reduced or the medication was discontinued. Although impulse-control disorders have been reported very rarely, impulse-control disorders may result in harm to the patient and others if not recognized. Consider dose reduction or stopping the medication if patient develops such urges while taking aripiprazole.
Skin
Severe Cutaneous Adverse Reactions (SCARs)
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP) are potentially life-threatening adverse drug reactions that have been reported with atypical antipsychotic exposure (see 8.5 Post-Market Adverse Reactions). SCARs commonly present as a combination of the following symptoms: extensive cutaneous rash or exfoliative dermatitis, fever, lymphadenopathy and possible eosinophilia. Discontinue ABILIFY MAINTENA if severe cutaneous adverse reactions occur.
7.1. Special Populations
7.1.1. Pregnancy
Teratogenic effects
There are no adequate and well-controlled studies of aripiprazole in pregnant women. It is not known whether aripiprazole can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity. In animal studies, aripiprazole demonstrated developmental toxicity, including possible teratogenic effects in rats and rabbits (see 16 Non-Clinical Toxicology).
Non-teratogenic effects
Neonates exposed to antipsychotic drugs, including aripiprazole, during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization. Prescribers need to be aware of the long-acting properties of ABILIFY MAINTENA. The clinical significance of aripiprazole administered before pregnancy or anytime during pregnancy is not known. ABILIFY MAINTENA should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus.
Labour and Delivery
The effect of aripiprazole on labour and delivery in humans is unknown.
7.1.2. Breastfeeding
Aripiprazole is excreted in human breast milk. A decision must be made whether to discontinue breastfeeding or to discontinue/abstain from ABILIFY MAINTENA therapy, taking in to account the benefit of breastfeeding for the child and the benefit of therapy for the woman.
7.1.3. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada for patients < 18 years of age; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
The safety and efficacy of ABILIFY MAINTENA in patients 65 years of age or older have not been established. Caution should be used when treating geriatric patients. In formal single-dose pharmacokinetic studies (with oral aripiprazole given in a single dose of 15 mg), aripiprazole clearance was 20% lower in elderly (>65 years) patients compared to younger adult patients (18 to 64 years). There was no detectable age effect, however, in the population pharmacokinetic analysis in schizophrenia patients. Also, the pharmacokinetics of aripiprazole after multiple doses in elderly patients appeared similar to that observed in young, healthy subjects. Nevertheless, geriatric patients generally have decreased cardiac, hepatic and renal function, and more frequent use of concomitant medication. The presence of multiple factors that might increase the pharmacodynamic response to aripiprazole, or cause poorer tolerance or orthostasis, should lead to careful monitoring during the initial dosing period for elderly patients.
Use in Elderly Patients with Dementia
Overall Mortality
Elderly patients with dementia treated with oral atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of 13 placebo-controlled trials of various atypical antipsychotic drugs (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. In three placebo-controlled studies of aripiprazole in elderly patients with Alzheimer’s disease (n=938; mean age: 82.4 years; range: 56-99 years), the rate of death in aripiprazole-treated patients was 3.5%, compared to a rate of 1.7% in the placebo group during or within 30 days after termination from the double-blind phase of the studies. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature.
ABILIFY MAINTENA is not indicated for the treatment of elderly patients with dementia (see 3 Serious Warnings and Precautions Box).
Cerebrovascular Adverse Events, Including Stroke in Elderly Patients with Dementia
In placebo-controlled clinical studies with oral aripiprazole (two flexible dose and one fixed dose study) of elderly patients with dementia, there was an increased incidence of cerebrovascular adverse events (e.g., stroke, transient ischemic attack), including fatalities, in aripiprazole-treated patients. In the fixed-dose study, there was a statistically significant dose-response relationship for cerebrovascular adverse events in patients treated with aripiprazole. Aripiprazole is not indicated for the treatment of patients with dementia (see 3 Serious Warnings and Precautions Box).
Frequent Treatment Emergent Adverse Events in Elderly Patients with Dementia
In the placebo-controlled studies of elderly patients with dementia (n=595 treated with oral aripiprazole, n=343 treated with placebo), the following treatment-emergent adverse events (TEAEs) were reported at an incidence of ≥3% and aripiprazole incidence at least twice that for placebo: lethargy [placebo 2%, aripiprazole 5%], somnolence (including sedation) [placebo 3%, aripiprazole 8%], and incontinence (primarily, urinary incontinence) [placebo 1%, aripiprazole 5%], excessive salivation (placebo 0%, aripiprazole 4%), and light-headedness (placebo 1%, aripiprazole 4%).
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use, including oral aripiprazole. Aspiration pneumonia is a common cause of morbidity and mortality in elderly patients, particularly in those with advanced Alzheimer’s dementia. Aripiprazole and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia. The emergence of difficulty swallowing or excessive somnolence could predispose patients to accidental injury or aspiration (see 7.1.4 Geriatrics, Use in Elderly Patients with Dementia).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The adverse event profile was similar across placebo-controlled trials of ABILIFY MAINTENA, administered once monthly, irrespective of the schizophrenia or bipolar I disorder indications. In the schizophrenia trials, the most frequently observed adverse events (AEs) reported in ≥ 5 % of patients in two double-blind pivotal maintenance clinical studies of ABILIFY MAINTENA were insomnia, weight increased, akathisia, headache, anxiety, weight decreased, nasopharyngitis and injection site pain. Overall, these adverse events were mild to moderate in severity and were similar to those in the placebo treated patients (Table 4). Based on the placebo-controlled trial of ABILIFY MAINTENA in the acute phase of schizophrenia, the most commonly observed adverse events associated with the use of aripiprazole in patients (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) were increased weight, akathisia, sedation, and injection site pain (Table 5). In the bipolar I disorder trial of ABILIFY MAINTENA, none of the adverse events in the double-blind, placebo-controlled phase were reported at an incidence ≥ 5 % of patients AND at least twice the incidence of placebo. Based on the placebo-controlled trial of ABILIFY MAINTENA in patients with bipolar I disorder, the most frequently observed adverse events reported in ≥ 5 % of ABILIFY MAINTENA patients and greater than placebo were weight increased, akathisia, anxiety, restlessness, and somnolence (Table 6).
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug. ABILIFY MAINTENA administered once monthly has been evaluated for safety in 2,649 adult patients in clinical trials in schizophrenia. Of the 2,649 adult schizophrenia patients exposed to ABILIFY MAINTENA, 2,567 patients have been treated with ABILIFY MAINTENA 400 mg/ 300 mg. Of the 2,649 patients exposed to ABILIFY MAINTENA, 1,316 patients have received at least 9 ABILIFY MAINTENA 400 mg/300 mg injections, (i.e., have been treated for at least 9 months), 941 patients have received at least 13 injections (i.e., have been treated for at least 12 months), and 632 patients received at least 26 injections (i.e., have been treated for 24 months). Table 4 and Table 5 present the adverse events reported at a rate of 2% or greater in the schizophrenia maintenance and acute treatment clinical trials, respectively.
ABILIFY MAINTENA has been evaluated for safety in 804 adult patients in clinical trials in bipolar I disorder, with approximately 530 patient-years of exposure to ABILIFY MAINTENA. A total of 419 patients were treated with ABILIFY MAINTENA for at least 7 consecutive injections (i.e., have been treated for at least 6 months) and 287 patients treated with ABILIFY MAINTENA had at least 13 consecutive injections (i.e., have been treated for at least 12 months). Table 6 presents the adverse events reported at a rate of 2% or greater in the bipolar I disorder clinical trial.
Table 4: Adverse Events occurring in 2% or more of patients with schizophrenia in both placebo and active controlled maintenance clinical trials
System Organ Class MedDRA Preferred Term | ABILIFY MAINTENA 400 mg/300 mg (N = 534) | Oral Aripiprazole 10-30 mg (N = 266) | Aripiprazole IM Depot 50 mg/25 mg (N = 131) | Placebo (N = 134) |
System Organ Class MedDRA Preferred Term | ABILIFY MAINTENA 400 mg/300 mg (N = 534) | Oral Aripiprazole 10-30 mg (N = 266) | Aripiprazole IM Depot 50 mg/25 mg (N = 131) | Placebo (N = 134) |
| n (%) | n (%) | n (%) | n (%) | |
| n (%) | n (%) | n (%) | n (%) | |
| Any TEAE | 389 (72.8) | 213 (80.1) | 106 (80.9) | 83 (61.9) |
| Gastrointestinal Disorders | ||||
| Diarrhea | 15 (2.8) | 9 (3.4) | 6 (4.6) | 3 (2.2) |
| Nausea | 10 (1.9) | 4 (1.5) | 3 (2.3) | 2 (1.5) |
| Toothache | 14 (2.6) | 13 (4.9) | 3 (2.3) | 3 (2.2) |
| Vomiting | 12 (2.2) | 4 (1.5) | 1 (0.8) | 3 (2.2) |
| General Disorders and Administration Site Conditions | ||||
| Fatigue | 11 (2.1) | 9 (3.4) | 2 (1.5) | 1 (0.7) |
| Injection site pain | 28 (5.2) | 6 (2.3) | 1 (0.8) | 5 (3.7) |
| Infections and Infestations | ||||
| Bronchitis | 7 (1.3) | 5 (1.9) | 5 (3.8) | 2 (1.5) |
| Influenza | 16 (3.0) | 11 (4.1) | 7 (5.3) | 2 (1.5) |
| Nasopharyngitis | 31 (5.8) | 25 (9.4) | 9 (6.9) | 7 (5.2) |
| Upper respiratory tract infection | 25 (4.7) | 11 (4.1) | 5 (3.8) | 3 (2.2) |
| Investigations | ||||
| Blood creatine phosphokinase increased | 10 (1.9) | 6 (2.3) | 5 (3.8) | 2 (1.5) |
| Blood pressure increased | 6 (1.1) | 1 (0.4) | 0 (0.0) | 3 (2.2) |
| Weight decreased | 35 (6.6) | 16 (6.0) | 12 (9.2) | 4 (3.0) |
| Weight increased | 50 (9.4) | 35 (13.2) | 7 (5.3) | 13 (9.7) |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 6 (1.1) | 1 (0.4) | 3 (2.3) | 0 (0.0) |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Arthralgia | 15 (2.8) | 4 (1.5) | 0 (0.0) | 1 (0.7) |
| Back pain | 16 (3.0) | 14 (5.3) | 15 (11.5) | 3 (2.2) |
| Pain in extremity | 11 (2.1) | 7 (2.6) | 2 (1.5) | 6 (4.5) |
| Nervous System Disorders | ||||
| Akathisia | 43 (8.1) | 18 (6.8) | 11 (8.4) | 8 (6.0) |
| Dizziness | 14 (2.6) | 6 (2.3) | 2 (1.5) | 4 (3.0) |
| Headache | 42 (7.9) | 30 (11.3) | 7 (5.3) | 7 (5.2) |
| Sedation | 13 (2.4) | 3 (1.1) | 1 (0.8) | 1 (0.7) |
| Somnolence | 14 (2.6) | 12 (4.5) | 2 (1.5) | 1 (0.7) |
| Tremor | 24 (4.5) | 9 (3.4) | 6 (4.6) | 2 (1.5) |
| Psychiatric Disorders | ||||
| Agitation | 9 (1.7) | 2 (0.8) | 0 (0.0) | 3 (2.2) |
| Anxiety | 35 (6.6) | 13 (4.9) | 10 (7.6) | 10 (7.5) |
| Depression | 7 (1.3) | 3 (1.1) | 0 (0.0) | 3 (2.2) |
| Insomnia | 58 (10.9) | 37 (13.9) | 18 (13.7) | 12 (9.0) |
| Psychotic disorder | 16 (3.0) | 8 (3.0) | 8 (6.1) | 9 (6.7) |
| Restlessness | 16 (3.0) | 4 (1.5) | 4 (3.1) | 3 (2.2) |
| Schizophrenia | 10 (1.9) | 5 (1.9) | 10 (7.6) | 5 (3.7) |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Cough | 14 (2.6) | 7 (2.6) | 5 (3.8) | 4 (3.0) |
| Vascular Disorders | ||||
| Hypertension | 7 (1.3) | 4 (1.5) | 4 (3.1) | 3 (2.2) |
Table 5: Adverse Events occurring in 2% or more of patients with schizophrenia in the Acute Phase Placebo controlled clinical trial and greater than placebo
System organ class MedDRA preferred term | Aripiprazole IM Depot 400/300mg (N=167) | Placebo (N=172) |
System organ class MedDRA preferred term | Aripiprazole IM Depot 400/300mg (N=167) | Placebo (N=172) |
| n (%) | n (%) | |
| n (%) | n (%) | |
| Gastrointestinal disorders | ||
| Abdominal discomfort | 4 (2.4) | 2 (1.2) |
| Constipation | 16 (9.6) | 12 (7.0) |
| Diarrhea | 5 (3.0) | 4 (2.3) |
| Dry mouth | 6 (3.6) | 4 (2.3) |
| Toothache | 9 (5.4) | 8 (4.7) |
| Vomiting | 5 (3.0) | 2 (1.2) |
| General disorders and administration site conditions | ||
| Fatigue | 4 (2.4) | 3 (1.7) |
| Injection site pain | 9 (5.4) | 1 (0.6) |
| Infections and infestations | ||
| Upper respiratory tract infection | 6 (3.6) | 3 (1.7) |
| Investigations | ||
| Weight decreased | 6 (3.6) | 4 (2.3) |
| Weight increased | 28 (16.8) | 12 (7.0) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 6 (3.6) | 2 (1.2) |
| Back pain | 7 (4.2) | 4 (2.3) |
| Musculoskeletal pain | 5 (3.0) | 2 (1.2) |
| Myalgia | 6 (3.6) | 1 (0.6) |
| Nervous system disorders | ||
| Akathisia | 19 (11.4) | 6 (3.5) |
| Dizziness | 6 (3.6) | 3 (1.7) |
| Sedation | 9 (5.4) | 2 (1.2) |
| Tremor | 5 (3.0) | 1 (0.6) |
| Psychiatric disorders | ||
| Insomnia | 8 (4.8) | 8 (4.7) |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 10 (6.0) | 10 (5.8) |
| Nasal congestion | 4 (2.4) | 2 (1.2) |
Table 6: Adverse Events occurring in 2% or more of patients with bipolar I disorder in the placebo controlled clinical trial and greater than placebo
System organ class MedDRA preferred term | ABILIFY MAINTENA 400/300mg (N=132) | Placebo (N=133) |
System organ class MedDRA preferred term | ABILIFY MAINTENA 400/300mg (N=132) | Placebo (N=133) |
| n (%) | n (%) | |
| n (%) | n (%) | |
| Blood and Lymphatic System Disorders | ||
| Anemia | 3 (2.3) | 0 (0.0) |
| Eye Disorders | ||
| Vision blurred | 3 (2.3) | 0 (0.0) |
| Gastrointestinal Disorders | ||
| Dry mouth | 4 (3.0) | 3 (2.3) |
| Infections and Infestations | ||
| Bronchitis | 3 (2.3) | 2 (1.5) |
| Influenza | 3 (2.3) | 2 (1.5) |
| Sinusitis | 5 (3.8) | 1 (0.8) |
| Urinary tract infection | 4 (3.0) | 2 (1.5) |
Injury, Poisoning and Procedural Complications | ||
| Procedural Pain | 4 (3.0) | 1 (0.8) |
| Investigations | ||
| Blood creatine phosphokinase increased | 3 (2.3) | 1 (0.8) |
| Weight increased | 31 (23.5) | 24 (18.0) |
| Metabolism and Nutrition Disorders | ||
| Increased appetite | 4 (3.0) | 1 (0.8) |
| Nervous System Disorders | ||
| Akathisia | 28 (21.2) | 17 (12.8) |
| Somnolence | 6 (4.5) | 1 (0.8) |
| Tremor | 3 (2.3) | 2 (1.5) |
| Psychiatric Disorders | ||
| Anxiety | 9 (6.8) | 6 (4.5) |
| Depression | 4 (3.0) | 3 (2.3) |
| Insomnia | 10 (7.6) | 10 (7.5) |
| Libido decreased | 3 (2.3) | 2 (1.5) |
| Restlessness | 6 (4.5) | 5 (3.8) |
Adverse Events Leading to Discontinuation of Treatment
In the schizophrenia trials, overall adverse reactions that led to discontinuation were similar for the aripiprazole-treated and placebo-treated patients in both the acute and maintenance phase studies. During double-blind treatment phase of the maintenance trials (Controlled Trials), TEAEs resulting in discontinuation of trial medication were experienced by 40/534 (7.5%) ABILIFY MAINTENA 400 mg/300 mg patients, 19/266 (7.1%) oral aripiprazole tablets 10-30 mg patients, 24/131 (18.3%) aripiprazole IM depot 50 mg/25 mg patients, and 18/134 (13.4%) placebo patients. In the acute schizophrenia trial, there was overall little difference in the incidence of discontinuations due to adverse reactions between ABILIFY MAINTENA-treated (4%) and placebo-treated (8%) patients. During the double-blind, placebo-controlled phase of the bipolar I disorder trial, fewer patients experienced a TEAE resulting in discontinuation in the ABILIFY MAINTENA group (23/132; 17.4%) compared to the placebo group (34/133; 25.6%). The following TEAEs led to discontinuation of IMP in more than 1 patient in either treatment group (ABILIFY MAINTENA vs placebo): mania (2.3% vs 8.3%), bipolar I disorder (1.5% vs 6.0%), bipolar disorder (3.8% vs 3.0%), depression (3.0% vs 2.3%), akathisia (1.5% vs 0.0%), affective disorder (0.0% vs 1.5%), and major depression (0.0% vs 1.5%).
Injection Site Adverse Events
The investigator rated pain, redness, swelling, and induration at the injection site at the same visits where patients assessed pain using a Visual Analog Scale (VAS; 0 mm = no pain to 100 mm = unbearably painful). Analyses of injection site assessments (investigator-rated and subject -reported VAS) were performed to evaluate the safety/tolerability of ABILIFY MAINTENA. Injection site assessments were completed after all injections during the ABILIFY MAINTENA schizophrenia and bipolar I disorder trials. The injection site adverse drug reaction profile was consistent across schizophrenia and bipolar studies. Across long-term trials, patient evaluations of injection site pain based on the VAS scale tended to lessen in frequency and intensity over time. In addition, overall, reactions were reported to be of mild to moderate severity. During the double-blind phase of schizophrenia maintenance studies, 37/534 (6.9%) ABILIFY MAINTENA 400 mg/300 mg patients, 7/266 (2.6%) oral aripiprazole tablets 10-30 mg patients, 1/131 (0.8%) aripiprazole IM depot 50 mg/25 mg IM patients, and 5/134 (3.7%) placebo patients experienced TEAEs related to the injection site. In the data from the acute phase double-blind placebo-controlled trial with ABILIFY MAINTENA in patients with schizophrenia, the percent of patients reporting any injection site-related adverse reaction was 5.4% for ABILIFY MAINTENA-treated patients. The mean intensity of injection pain reported by patients using a visual analog scale (0=no pain to 100=unbearably painful) was minimal in patients receiving ABILIFY MAINTENA (7.1 after first injection, and 7.7 after last injection). In the data from the double-blind, placebo-controlled phase in patients with bipolar I disorder, the percentage of patients reporting injection site-related adverse reactions was similar between ABILIFY MAINTENA (0.8%) and placebo (1.5%).
Table 7: Investigator assessments of pain, redness, swelling and induration at the injection site and Patient VAS scores
Treatment Group Dose (n) | Absence of Investigator Rated Pain, Redness, Swelling, and Induration at the Injection Site (% of patients)* | Mean VAS (patient rated pain from 0 – 100mm) | ||
|---|---|---|---|---|
Treatment Group Dose (n) | Absence of Investigator Rated Pain, Redness, Swelling, and Induration at the Injection Site (% of patients)* | Mean VAS (patient rated pain from 0 – 100mm) | ||
First Injection | Last Injection | First Injection | Last Injection | |
First Injection | Last Injection | First Injection | Last Injection | |
| 38-week ABILIFY MAINTENA double-blind, active-controlled trial in adult patients with schizophrenia | ||||
| Double-blind, Active-controlled Phase | ||||
ABILIFY MAINTENA 400 mg/300 mg (n=265) | 81.4 – 98.1 | 88.3 – 98.9 | 5.6 | 3.7 |
Oral aripiprazole 10-30 mg (n=266) | 83.3 – 98.5 | 90.2 – 99.6 | 4.9 | 3.5 |
Aripiprazole IM Depot 50 mg/25 mg (n=131) | 90.7 – 99.2 | 90.0 – 99.2 | 3.3 | 2.4 |
| 52-week ABILIFY MAINTENA double-blind, placebo-controlled trial in adult patients with schizophrenia | ||||
| IM Depot Stabilization Phase (Open Label)** | ||||
ABILIFY MAINTENA 400 mg/300 mg (n=403) | 75.3 – 96.2 | 77.3 – 97.0 | 6.0 | 4.5 |
| Double-blind, Placebo-controlled Phase | ||||
ABILIFY MAINTENA 400 mg/300 mg (n=269) | 80.1 – 98.1 | 84.4 – 98.5 | 5.1 | 4.0 |
| Placebo (n=134) | 72.2 – 97.7 | 77.3 – 97.7 | 5.1 | 4.9 |
| 12-week ABILIFY MAINTENA double-blind, placebo-controlled trial in the acute phase of schizophrenia | ||||
ABILIFY MAINTENA 400 mg/300 mg (n=167) | 95.1-100 | 99.2-100 | 7.1 | 7.7 |
| Placebo (n=172) | 94.7-100 | 98.4-100 | 5.7 | 8.6 |
| 52-week ABILIFY MAINTENA double-blind, placebo-controlled trial in patients with bipolar I disorder | ||||
| Double-blind, Placebo-controlled Phase | ||||
| ABILIFY MAINTENA | 81.8-100 | 87.1-100 | 5.2 | 4.0 |
| 400 mg/300 mg (n=132) | ||||
| Placebo (n=133) | 81.2-100 | 85.0-100 | 5.7 | 5.8 |
*Range of percent is based on rating in the 4 domains (pain, redness, swelling, and induration)
** The open-label analyses were done to understand the injection site reaction parameters after initiation of ABILIFY MAINTENA as well as during its continued use in the double-blind, placebo-controlled phase.
In an open label study comparing bioavailability of ABILIFY MAINTENA administered in the deltoid or gluteal muscle, injection site related reactions were observed in both groups at approximately equal rates and the majority were mild and improved on subsequent injections.
Extrapyramidal Symptoms (EPS)
The table below presents the percentage of patients experiencing treatment emergent EPS and EPS related events during the double-blind phases of the 38-and 52-week trials in schizophrenia.
Table 8: Patients experiencing EPS and EPS related Events in the schizophrenia maintenance trials
ABILIFY MAINTENA 400 mg/300 mg | Oral aripiprazole 10-30 mg | Aripiprazole IM Depot 50 mg/25 mg (n=131) | Placebo | |
|---|---|---|---|---|
| Treatment Emergent EPS and EPS related events | 18.4% | 11.7% | 12.2% | 9.7% |
| Akathisia | 8.2% | 6.8% | 8.4% | 6.0% |
| Parkinsonism | 6.9% | 4.1% | 5.3% | 3.0% |
There was minimal variation in EPS symptoms during the double-blind phases of the schizophrenia trials, as assessed by mean changes from baseline in the Simpson Angus Scale (SAS), Abnormal Involuntary Movement Scale (AIMS), and Barnes Akathisia Rating Scale (BARS) rating scales. Although there were statistically significant differences between the mean change from baseline in the BARS global score between ABILIFY MAINTENA 400 mg/300 mg and oral aripiprazole tablets 10-30 mg (Weeks 8 and 38) and between ABILIFY MAINTENA 400 mg/300 mg and aripiprazole IM depot 50 mg/25 mg (Week 8, Week 12 and Week 36), the mean changes were not considered to be clinically relevant.
Similar results were observed in the 12-week placebo-controlled study in the acute phase of schizophrenia, with akathisia occurring in 11.4% of the patients on ABILIFY MAINTENA compared to 3.5% of placebo patients and parkinsonism occurring in 5.4% of ABILIFY MAINTENA patients compared to 2.3% of placebo patients. During the double-blind, placebo-controlled phase of the bipolar I disorder trial, 36/132 (27.3%) ABILIFY MAINTENA-treated patients and 22/133 (16.5%) placebo-treated patients had treatment-emergent EPS and EPS-related AEs. In the ABILIFY MAINTENA (vs. placebo) group, EPS and EPS-related events reported by ≥ 2% of patients were akathisia and psychomotor hyperactivity events (22.0% vs 12.8%), parkinsonism events (5.3% vs 3.8%), dyskinetic (2.3% vs 1.5%), and dystonic events (2.3% vs 0.0%). The most frequently reported treatment-emergent EPS and EPS-related AE was akathisia with 28/132 (21.2%) ABILIFY MAINTENA-treated patients and 17/133 (12.8%) placebo-treated patients experiencing an event. One ABILIFY MAINTENA-treated and no placebo-treated patients experienced a serious adverse event (SAE) of akathisia and 2 ABILIFY MAINTENA-treated patients were discontinued due to akathisia. There were no other EPS-related SAEs and no other TEAEs leading to discontinuation reported.
Dystonia
Class Effect-Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs. An elevated risk of acute dystonia is observed in males and younger age groups.
Weight
One placebo-controlled trial with ABILIFY MAINTENA was conducted in hospitalized patients in the acute phase of schizophrenia, the mean change in body weight was +2.8 kg (N=144) in the ABILIFY MAINTENA-treated patients and +0.8 kg (N=141) in the placebo-treated patients, as assessed in patients with a median exposure of 85 days and a post baseline weight result at the last visit. The incidence of weight gain of ≥ 7% from baseline to last visit was 22% for the ABILIFY MAINTENA 400 mg/300 mg group, and 9% for the placebo group. During double-blind treatment in the maintenance schizophrenia trials (Controlled Trials), TEAEs related to weight were reported for 87/534 (16.3%) ABILIFY MAINTENA 400 mg/300 mg patients, 52/266 (19.5%) oral aripiprazole tablets 10-30 mg patients, 19/131 (14.5%) aripiprazole IM depot 50 mg/25 mg patients, and 17/134 (12.7%) placebo patients. TEAEs related to weight that were reported included increased weight, decreased weight, overweight, and edema. During the double-blind, active-controlled phase of the 38-week ABILIFY MAINTENA schizophrenia trial, the incidence of weight gain of ≥ 7% from baseline to last visit was 9.5% for the ABILIFY MAINTENA 400 mg/300 mg group, 11.7% for oral aripiprazole tablets 10-30 mg group and 4.6% for the aripiprazole IM depot 50 mg/25 mg group. The incidence of weight loss of ≥ 7% from baseline to last visit was 10.2% for ABILIFY MAINTENA 400 mg/300 mg, 4.5% for oral aripiprazole tablets 10-30 mg, and 9.9% for aripiprazole IM depot 50 mg/25 mg. During double-blind treatment, mean change in body weight from baseline to last visit was -0.2kg for ABILIFY MAINTENA, +0.7kg for oral aripiprazole tablets and -1.1 for aripiprazole IM depot 50 mg/25 mg. Overall in the maintenance clinical trials there was no difference in the incidence of weight gain between ABILIFY MAINTENA and placebo. During the double-blind, placebo-controlled phase of the 52-week ABILIFY MAINTENA schizophrenia trial, the incidence of weight gain of ≥ 7% from baseline to last visit was similar between ABILIFY MAINTENA and placebo: 6.4% for the ABILIFY MAINTENA 400 mg/300 mg group and 5.2% for the placebo group. The incidence of weight loss of ≥ 7% from baseline to last visit was 6.4% for the ABILIFY MAINTENA 400 mg/300 mg group and 6.7% for the placebo group. During double-blind treatment, mean change in body weight from baseline to last visit was -0.2kg for ABILIFY MAINTENA and -0.4kg for placebo. During the double-blind, placebo-controlled phase of the bipolar I disorder trial, the incidence of weight gain ≥ 7% at any time was reported for 18.0% for ABILIFY MAINTENA-treated patients and 12.9% for placebo- treated patients; the incidence of weight loss ≥ 7% at any time was reported for 9.4% ABILIFY MAINTENA-treated patients and 12.1% placebo-treated patients. At the last visit, the incidence of potentially clinically relevant weight gain was 13.3% ABILIFY MAINTENA-treated patients and 12.1% placebo-treated patients; the incidence of weight loss ≥ 7% at last visit was reported for 5.5% ABILIFY MAINTENA-treated patients and 10.6% placebo-treated patients. The mean change (SD) from baseline at Week 52 was 1.3 (5.9) kg for ABILIFY MAINTENA-treated and 1.5 (6.1) kg for placebo-treated patients; and at last visit was 0.9 (5.3) kg for ABILIFY MAINTENA-treated and 0.0 (5.9) kg for placebo-treated patients.
QT Interval
During double-blind treatment in patients with schizophrenia, 1/534 (0.2%) ABILIFY MAINTENA 400 mg/300 mg patients had a TEAE related to QT interval change (prolonged ECG QT). In the double-blind, placebo-controlled phase of the bipolar I disorder trial and the open-label trial, there were no QT interval-related TEAEs reported. In the clinical trials of treatment with ABILIFY MAINTENA across indications, the incidence of QT prolongation was comparable to placebo. As with other antipsychotics, aripiprazole should be used with caution in patients with a family history of QT prolongation.
Prolactin
Changes in prolactin levels were comparable across trials, irrespective of indication (schizophrenia or bipolar I disorder), and there were no clinically relevant mean changes from baseline to the last visit with regard to prolactin levels during the double-blind treatment phase of either trial. In the double-blind active-controlled phase of the 38-week schizophrenia trial, from baseline to last visit, there was a mean decrease in prolactin levels in the ABILIFY MAINTENA 400 mg/300 mg group (−0.33 ng/mL) compared with a mean increase in the oral aripiprazole tablets 10-30 mg group (0.79 ng/mL) and aripiprazole IM depot 50 mg/25 mg (1.11 ng/mL) groups. The incidence for ABILIFY MAINTENA 400 mg/300 mg patients with prolactin levels >1 time the upper limit of normal range (ULN) at any assessment was 5.4% compared with 3.5% of oral aripiprazole tablets 10-30 mg, and 4.7% of aripiprazole IM depot 50 mg/25 mg patients, with a higher incidence in male patients than female patients in each treatment group. In the double-blind placebo-controlled phase of the 52-week schizophrenia trial, from baseline to last visit, there was a mean decrease in prolactin levels in the ABILIFY MAINTENA 400 mg/300 mg group (−0.38 ng/mL) compared with a mean increase in the placebo group (1.67 ng/mL). The incidences of ABILIFY MAINTENA 400 mg/300 mg patients with prolactin levels >1 time the upper limit of normal range (ULN) was 1.9% compared to 7.1% for placebo patients. In the double-blind, placebo-controlled phase of the bipolar I disorder trial, the mean changes from baseline to last visit in prolactin were minimal in the ABILIFY MAINTENA 400 mg/300 mg group (0.15 ng/mL) compared to placebo (3.00 ng/mL) and none of the changes were considered to be clinically meaningful. There were no clinically meaningful differences in the incidence of prolactin levels above the ULN between treatment groups and no incidence of > 3 × ULN reported during the double-blind, phase of this trial. No clinically meaningful differences in shifts in prolactin between treatment groups or gender were reported. During the double-blind phase, no ABILIFY MAINTENA-treated and 0.8% of placebo-treated patients experienced the prolactin-related TEAE of hyperprolactinemia.
8.3. Less Common Clinical Trial Adverse Reactions
Treatment emergent adverse events listed below were reported by less than 2% of patients and at least as frequently in the placebo group on ABILIFY MAINTENA during the randomization phase of the schizophrenia clinical trials.
Blood and Lymphatic System Disorders: Bicytopenia, lymphadenopathy, neutropenia, thrombocytopenia. Cardiac Disorders: Acute myocardial infarction, atrioventricular block first degree, cardiac failure congestive, ventricular extrasystoles. Ear and Labyrinth Disorders: Deafness, vertigo. Eye Disorders: Conjunctivitis allergic, eye irritation, eye pain, eyelid ptosis, oculogyric crisis, vision blurred, photophobia. Gastrointestinal Disorders: Abdominal pain, abdominal pain upper, anorectal discomfort, aphthous ulcer, colitis, dental caries, diverticulum, dyspepsia, dysphagia, frequent bowel movements, gastritis, gastrooesophageal reflux disease, gingival oedema, gingival pain, gingivitis, hemorrhoids, inguinal hernia, loose tooth, periodontitis, poor dental condition, salivary hypersecretion, tongue disorder, tooth impacted, tooth loss. General Disorders and Administration Site Conditions: Asthenia, chest discomfort, gait disturbance, influenza like illness, infusion site hematoma, infusion site swelling, injection site discomfort, injection site pruritus, injection site induration, injection site reaction, injection site swelling, oedema peripheral, pain, sluggishness, suprapubic pain, thirst, vessel puncture site hematoma, vessel puncture site pain. Hepatobiliary Disorders: Cholecystitis chronic, cholelithiasis, hepatic cirrhosis, hepatic steatosis, hepatosplenomegaly. Immune System Disorders: Drug hypersensitivity. Infections and Infestations: Acarodermatitis, anal abscess, appendicitis perforated, cellulitis, cystitis, ear infection, Escherichia urinary tract infection, folliculitis, fungal infection, fungal skin infection, furuncle, gastroenteritis, gastroenteritis viral, herpes virus infection, herpes zoster, hordeolum, impetigo, lice infestation, localized infection, mastitis, oral candidiasis, pharyngitis, pharyngitis streptococcal, pilonidal disease, pneumonia, respiratory tract infection, viral rhinitis, subcutaneous abscess, tinea pedis, tooth abscess, tooth infection, urinary tract infections, vaginal infection, varicella, viral infection, vulvovaginal mycotic infection. Injury, Poisoning and Procedural Complications: Accident, ankle fracture, carbon monoxide poisoning, contusion, face injury, fall, foot fracture, gun shot wound, injury, joint dislocation, ligament sprain, multiple injuries, muscle injury, muscle strain, procedural pain, radius fracture, skeletal injury, skin abrasion, skin laceration, thermal burn, tooth fracture, toxicity to various agents, wound. Investigations: Alanine aminotransferase increased, blood alkaline phosphatase increased, blood bilirubin increased, blood cholesterol decreased, blood glucose decreased, blood glucose increased, blood insulin increased, blood lactate dehydrogenase increased, blood prolactin decreased, blood triglycerides decreased, blood triglycerides increased, electrocardiogram abnormal, electrocardiogram QT prolonged, electrocardiogram T wave amplitude decreased, electrocardiogram T wave inversion, gamma-glutamyltransferase increased, glucose urine present, glycosylated hemoglobin increased, heart rate decreased, hepatic enzyme increased, liver function test abnormal, neutrophil count decreased, protein urine, waist circumference increased, white blood cell count decreased, white blood cells urine. Metabolism and Nutrition Disorders: Appetite disorder, diabetes mellitus, gout, hypercholesterolemia, hyperglycemia, hyperinsulinemia, hyperlipidemia, hypertriglyceridemia, hyperuricemia, hypoglycemia, increased appetite, overweight, type 2 diabetes mellitus. Musculoskeletal and Connective Tissue Disorders: Arthritis, joint swelling, muscle rigidity, muscle spasms, muscle tightness, muscle twitching, musculoskeletal pain, musculoskeletal stiffness, myalgia, nuchal rigidity, rotator cuff syndrome, trismus. Neoplasms Benign Malignant and Unspecified: Basal cell carcinoma, breast fibroma, pancreatic carcinoma. Nervous System Disorders: Bradykinesia, cogwheel rigidity, disturbance in attention, dizziness, drooling, dyskinesia, dystonia, extrapyramidal disorder, hypersomnia, hypoesthesia, migraine, movement disorder, oromandibular dystonia, parkinsonism, parosmia, poor quality sleep, psychomotor hyperactivity, restless legs syndrome, sinus headache, syncope, tension headache. Psychiatric Disorders: Abnormal dreams, affect lability, apathy, bruxism, bulimia nervosa, delusion, dysphoria, hallucination auditory, hypersexuality, hyposomnia, libido decreased, middle insomnia, mood altered, nightmare, panic attack, panic reaction, sleep disorder, suicidal ideation, suicide attempt, tension. Renal and Urinary Disorders: Glycosuria, micturition urgency, nephrolithiasis, pollakiuria. Reproductive System and Breast Disorders: Adnexa uteri pain, breast mass, breast tenderness, erectile dysfunction, galactorrhoea, gynecomastia, ovarian cyst, vulvovaginal dryness. Respiratory Thoracic and Mediastinal Disorders: Acute respiratory distress syndrome, dysphonia, dyspnoea, epistaxis, nasal septum deviation, oropharyngeal pain, paranasal sinus hypersecretion, respiratory tract congestion, rhinalgia, rhinitis allergic, sinus congestion, wheezing. Skin and Subcutaneous Tissue Disorders: Acne, blister, dry skin, eczema, erythema, hyperkeratosis, pruritus, psoriasis, rash macular, rosacea, skin induration, skin lesion, skin striae, urticaria. Vascular Disorders: Orthostatic hypotension. Adverse Events reported with Oral Aripiprazole Short-Term, Placebo-Controlled Trials of Adult Patients with Schizophrenia Based on a pool of five placebo-controlled trials (four 4-week and one 6-week) in which aripiprazole was administered orally in doses ranging from 2 to 30 mg/day the only commonly observed adverse event associated with the use of oral aripiprazole in patients with schizophrenia (incidence of 5% or greater and aripiprazole incidence at least twice that for placebo) was akathisia (placebo 4%; aripiprazole 8%).
Long-Term, Double-Blind, Placebo-Controlled Trials in Adult Patients with Schizophrenia
The adverse events reported in a 26-week, double-blind trial comparing oral aripiprazole and placebo in adult patients with schizophrenia were generally consistent with those reported in the short-term, placebo-controlled trials, except for a higher incidence of tremor [8% (12/153) for oral aripiprazole vs. 2% (3/153) for placebo]. In this study, the majority of the cases of tremor were of mild intensity (8/12 mild and 4/12 moderate), occurred early in therapy (9/12 ≤49 days), and were of limited duration (7/12 ≤10 days). Tremor infrequently led to discontinuation (<1%) of oral aripiprazole. In addition, in a long-term (52-week), active-controlled study, the incidence of tremor for oral aripiprazole was 5% (40/859).
Short-Term, Placebo-Controlled Trials of Adult Patients with Bipolar Disorder
The following findings are based on a pool of 3-week, placebo-controlled, bipolar mania trials in which aripiprazole was administered orally at doses of 15 or 30 mg/day. Overall, in patients with bipolar mania, there was little difference in the incidence of discontinuation due to adverse events between aripiprazole-treated (11%) and placebo-treated (10%) patients. The types of adverse events that led to discontinuation were similar between the aripiprazole and placebo-treated patients. Akathisia, the most common adverse event leading to discontinuation in the aripiprazole group, led to withdrawal of 2% of aripiprazole-treated patients and 0.3% of patients on placebo. Commonly reported adverse events associated with the use of aripiprazole in patients with bipolar mania (incidence of 5% or greater and aripiprazole incidence at least twice that of placebo) was, for aripiprazole and placebo (respectively): akathisia: 13/917 and 4/753, sedation: 8/917 and 3/753, restlessness: 6/917 and 2/753, and extrapyramidal disorder: 5/917 and 2/753.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
No clinically relevant mean changes from baseline in serum chemistry, hematology, urinalysis, or other laboratory test (insulin, fasting insulin) results were observed during any of the clinical trials with ABILIFY MAINTENA. In both schizophrenia maintenance trials differences in the mean (± SD) change from the double-blind treatment phase baseline at the last visit in WBC, fasting glucose, lipids, and CPK levels were negligible between the ABILIFY MAINTENA 400 mg/300 mg group, and oral aripiprazole tablets 10-30 mg group, aripiprazole IM depot 50 mg/25 mg group or placebo groups and were considered to be of no clinical relevance. Mean changes in total CPK have been associated with NMS, and higher percentages of elevated creatine phosphokinase have been observed in oral aripiprazole-treated adult patients compared to placebo-treated patients in short-term and long-term clinical trials; however mean decreases were noted for ABILIFY MAINTENA 400 mg/300 mg in the active controlled trial and the differences between the ABILIFY MAINTENA and placebo groups were negligible in the placebo-controlled maintenance trial. In the acute placebo-controlled trial no clinically relevant mean changes from baseline in serum chemistry, hematology, urinalysis or other laboratory tests were observed during the acute treatment phase. In the bipolar I disorder placebo-controlled and open label trials, no subject met the criteria for Hy’s law relative to laboratory values of potential clinical relevance. In clinical studies of oral aripiprazole, in a long-term (26-week) placebo-controlled trial in adult patients with schizophrenia there were no clinically important differences between the aripiprazole and placebo patients in the mean change from baseline in prolactin, fasting glucose, triglyceride, HDL, LDL, and total cholesterol measurements. Higher percentages of elevated creatine phosphokinase were observed in aripiprazole-treated adult patients compared to placebo-treated patients in short-term and long-term clinical trials. The most common AEs that were temporally associated with elevated CPK levels were musculoskeletal stiffness, myalgia, chest pain, fall, and muscle rigidity.
8.5. Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of oral aripiprazole or ABILIFY MAINTENA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The adverse events listed below were reported during the post-marketing use of aripiprazole. Eye Disorders: Diplopia Gastrointestinal Disorders: Pancreatitis Hepatobiliary Disorders: Hepatic failure, hepatitis, jaundice Investigations: Aspartate aminotransferase (AST or SGOT) increased, blood glucose fluctuation, blood glucose increased, gamma-glutamyltransferase (GGT) increased Metabolism and Nutrition Disorders: Anorexia, hyponatremia Nervous System Disorders: Generalized tonic-clonic seizure, restless legs syndrome, speech disorder Psychiatric Disorders: Hypersexuality, impulse-control disorders, pathological gambling Renal and Urinary Disorders: Urinary retention Respiratory, Thoracic, and Mediastinal Disorders: Hiccups Skin and Subcutaneous Tissue Disorders: Allergic reaction (e.g., anaphylactic reaction, angioedema, laryngospasm, oropharyngeal spasm), alopecia, drug reaction with eosinophilia and systemic symptoms (DRESS), hyperhidrosis Although a causal relationship has not been established, cases of suicide attempt, suicidal ideation, and completed suicide have been reported post marketing. As with other antipsychotics, sudden death, torsades de pointes, ventricular tachycardia, arrhythmia, cardiopulmonary arrest and QT prolongation have been reported during treatment with oral aripiprazole. These events during aripiprazole treatment have been very rare or isolated. Many of the patients had pre-existing cardiovascular disease, were on concomitant medications known to prolong the QT interval, had risk factors for QT prolongation, took an overdose of oral aripiprazole, and/or were morbidly obese. Very rarely, QT prolongation has been reported in the absence of confounding factors. Isolated cases of Serotonin Syndrome have been reported with the concomitant use of aripiprazole and serotonergic drugs such as Serotonin-Norepinephrine Reuptake Inhibitor (SNRI) and Selective Serotonin Reuptake Inhibitor (SSRI). Complex sleep-related behaviours such as somnambulism and sleep-related eating disorder have been associated with the use of atypical antipsychotic drugs, including aripiprazole. In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents, including aripiprazole. Agranulocytosis has also been reported. Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting ABILIFY MAINTENA and then periodically throughout treatment (see 7 Hematologic; 7 Monitoring and Laboratory Tests). Atypical antipsychotic drugs, including aripiprazole, have been associated with cases of sleep apnea, with or without concomitant weight gain. In patients who have a history of or are at risk for sleep apnea, aripiprazole should be prescribed with caution.
9. Drug Interactions
9.2. Drug Interactions Overview
No specific drug interaction studies have been performed with ABILIFY MAINTENA. The information below was obtained from studies with oral aripiprazole. If aripiprazole is administered concomitantly with medicinal products known to cause QT prolongation or electrolyte imbalance, caution should be used.
9.3. Drug-Behaviour Interactions
Alcohol/CNS Drugs Given the primary CNS effects of aripiprazole, as with most psychoactive medications, combination use of aripiprazole with alcohol or other CNS drugs with overlapping undesirable effects such as sedation, should be avoided.
Smoking
Aripiprazole is not metabolized by CYP1A enzymes. Therefore, no dosage adjustment is required for smokers (see 10.3 Pharmacokinetics, Smoking).
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies with oral aripiprazole, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 9: Established or Potential Drug-Drug Interactions
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Common name | Source of Evidence | Effect | Clinical comment |
| Antihypertensive agents | |||
| --- | T | Due to its α1-adrenergic receptor antagonism, aripiprazole has the potential to enhance the effect of certain antihypertensive agents | --- |
| Strong CYP2D6 inhibitors | |||
Quinidine fluoxetine, paroxetine, bupropion | CT | Aripiprazole: AUC ↑107% dehydro-aripiprazole: AUC ↓32% Cmax ↓47% | Dosage adjustments are recommended for concomitant use of strong CYP2D6 inhibitors with ABILIFY MAINTENA (see 4.2 Recommended Dose and Dosage Adjustment - Table 1). Upon discontinuation of the CYP2D6 inhibitor, the dosage of ABILIFY MAINTENA should be increased to the dose prior to the initiation of the concomitant therapy. |
| Strong CYP3A4 inhibitors | |||
| ketoconazole itraconazole, HIV protease inhibitors | CT | Aripiprazole: AUC ↑63% Cmax ↑37% dehydro-aripiprazole: AUC ↑77% Cmax ↑43% | Dosage adjustments are recommended for concomitant use of strong CYP3A4 inhibitors with ABILIFY MAINTENA (see 4.2 Recommended Dose and Dosage Adjustment - Table 1). Upon discontinuation of the CYP3A4 inhibitor, the dosage of ABILIFY MAINTENA should be increased to the dose prior to the initiation of the concomitant therapy. |
| Weak CYP3A4 inhibitors or Weak CYP2D6 inhibitors | |||
| Diltiazem, escitalopram | T | Modest increases in plasma aripiprazole concentrations may be expected. | --- |
| CYP3A4 Inducers | |||
Carbamazepine, rifampicin, rifabutin, phenytoin, phenobarbital, primidone, efavirenz, nevirapine, St. John's Wort | CT | Aripiprazole: AUC ↓73% Cmax ↓68% dehydro-aripiprazole: AUC ↓71% Cmax ↓69% | Avoid concomitant use of CYP3A4 inducers with ABILIFY MAINTENA for more than 14 days because the blood levels of aripiprazole are decreased and may be below the effective levels (see 4.2 Recommended Dose and Dosage Adjustment - Table 1). |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Potential for other drugs to affect aripiprazole
Aripiprazole is metabolized by multiple pathways involving the CYP2D6 and CYP3A4 enzymes and dosage adjustments are recommended (see 4.2 Recommended Dose and Dosage Adjustment - Table 1).
Potential for Aripiprazole to Affect Other Drugs
In clinical studies, oral doses of 10-30 mg/day had no significant effect on the metabolism of substrates of CYP2D6 (dextromethorphan/3-methoxymorphinan ratio), 2C9 (warfarin), 2C19 (omeprazole), and 3A4 (dextromethorphan). Additionally, aripiprazole and dehydro-aripiprazole did not show potential for altering CYP1A2-mediated metabolism in vitro. Thus, ABILIFY MAINTENA is unlikely to cause clinically important medicinal product interactions mediated by these enzymes. No dosage adjustment of dextromethorphan, warfarin, omeprazole, escitalopram, or venlafaxine is required when co-administered with ABILIFY MAINTENA.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
The mechanism of action of aripiprazole, as with other drugs having efficacy in schizophrenia or bipolar I disorder is unknown. It has been proposed that the efficacy of aripiprazole may be mediated through a combination of partial agonist activity at D2 and 5-HT1A receptors and antagonist activity at 5-HT2A receptors; however, the clinical relevance of these interactions has not been established. Actions at receptors other than D2, 5-HT1A, and 5-HT2A may explain some of the other adverse reactions of aripiprazole (e.g., the orthostatic hypotension observed with aripiprazole may be explained by its antagonist activity at adrenergic alpha1 receptors). The clinical relevance of these receptor interactions with aripiprazole is unknown.
10.2. Pharmacodynamics
Aripiprazole exhibits high affinity for dopamine D2 and D3 and serotonin 5-HT1A and 5-HT2A receptors (Ki values of 0.34 nM, 0.8 nM, 1.7 nM, and 3.4 nM, respectively) and has moderate affinity for dopamine D4, serotonin 5-HT2C and 5-HT7, α1-adrenergic, histamine H1 receptors (Ki values of 44 nM, 15 nM, 39 nM, 57 nM and 61 nM, respectively), and the serotonin reuptake site (Ki=98 nM). Aripiprazole also displays 5-HT1A partial agonist and 5-HT2A antagonist activity in nonclinical studies.
10.3. Pharmacokinetics
Overview:
The activity of ABILIFY MAINTENA is presumably primarily due to the parent drug, aripiprazole, and to a lesser extent, to its major metabolite, dehydro-aripiprazole, which has been shown to have affinities for D2 receptors similar to the parent drug and represents approximately 29% of the parent drug exposure in plasma at steady state.
Absorption: Aripiprazole absorption into the systemic circulation is slow and prolonged following ABILIFY MAINTENA administration due to low solubility of aripiprazole particles.
Following a single dose administration of ABILIFY MAINTENA in the deltoid and gluteal muscle, the extent of absorption (AUC) was similar for both injection sites, but the rate of absorption (Cmax) was higher following administration to the deltoid. Following multiple intramuscular doses, the plasma concentrations of aripiprazole gradually rise to a maximum plasma concentration at a median Tmax of 7 days for the gluteal muscle and 4 days for the deltoid muscle. Approximate dose-proportional increases in aripiprazole and dehydro-aripiprazole concentrations and AUC parameters are observed after monthly ABILIFY MAINTENA injections of 400 mg and 300 mg and steady state aripiprazole plasma concentrations for the typical subject were attained by the fourth monthly injection for both sites of administration. When the one injection start is administered and oral aripiprazole is not administered prior to initiation of ABILIFY MAINTENA, the predicted median aripiprazole concentration reaches the lower threshold of therapeutic window by Day 3 after ABILIFY MAINTENA administration, and remains very near the lower threshold over the full dosing interval. In contrast, when oral aripiprazole is administered prior to initiation of ABILIFY MAINTENA with the one injection start, median aripiprazole concentration is maintained above or reaches the lower threshold of therapeutic window by Day 1-2, and is maintained above threshold of therapeutic window for the first 28 days after the first administration of ABILIFY MAINTENA. Modelling and simulation studies show that this is probably also the case when the two injection start is administered with or without administration of oral aripiprazole prior to initiation of ABILIFY MAINTENA.
Distribution: The steady-state volume of distribution of aripiprazole following intravenous administration is high (404 L or 4.9 L/kg), indicating extensive extravascular distribution. At therapeutic concentrations, aripiprazole and dehydro-aripiprazole are greater than 99% bound to serum proteins, binding primarily to albumin.
Metabolism: Aripiprazole is extensively metabolised by the liver primarily by three biotransformation pathways: dehydrogenation, hydroxylation, and N-dealkylation. Based on in vitro studies, CYP3A4 and CYP2D6 enzymes are responsible for dehydrogenation and hydroxylation of aripiprazole, and N-dealkylation is catalysed by CYP3A4. Aripiprazole is the predominant medicinal product moiety in systemic circulation. After multiple dose administration of ABILIFY MAINTENA, dehydro-aripiprazole, the active metabolite, represents about 29% of aripiprazole AUC in plasma.
CYP2D6 Poor Metabolizers
Approximately 8% of Caucasians lack the capacity to metabolize CYP2D6 substrates and are classified as poor metabolizers (PM), whereas the rest are extensive metabolizers (EM). PMs have about an 80% increase in aripiprazole exposure and about a 30% decrease in exposure to the active metabolite compared to EMs, resulting in about a 60% higher exposure to the total active moieties from a given dose of aripiprazole compared to EMs. The mean elimination half-life for aripiprazole is about 75 hours in EMs and 146 hours in PMs. Based on population PK analyses, clearance of aripiprazole is reduced by approximately 51% to 1.88 L/h in CYP2D6 PMs for all formulations (oral, ABILIFY MAINTENA), compared to clearance of 3.71 L/h in EMs. Co-administration of aripiprazole with known inhibitors of CYP2D6, like quinidine in EMs, results in a 112% increase in aripiprazole plasma exposure, and dose adjustment is needed (see 9.4 Drug-Drug Interactions). Aripiprazole does not inhibit or induce the CYP2D6 pathway (see 4.1 Dosing Considerations). Elimination: After multiple dose administration of 300 mg or 400 mg of ABILIFY MAINTENA, the mean aripiprazole terminal elimination half-life is 29.9-46.5 days. Special Populations and Conditions Geriatrics: In formal single-dose pharmacokinetic studies (with oral aripiprazole given in a single dose of 15 mg), aripiprazole clearance was 20% lower in elderly (≥65 years) patients compared to younger adult patients (18 to 64 years). There was no detectable age effect, however, in the population pharmacokinetic analysis in patients with schizophrenia. Also, the pharmacokinetics of aripiprazole after multiple doses in elderly patients appeared similar to that observed in young, healthy subjects (see 7.1.4 Geriatrics, 4.1 Dosing Considerations). Sex: Cmax and AUC of aripiprazole and its active metabolite, dehydro-aripiprazole, are 30 to 40% higher in women than in men, and correspondingly, the apparent oral clearance of aripiprazole is lower in women. These differences, however, are largely explained by differences in body weight (25%) between men and women. No dosage adjustment is recommended based on gender. Ethnic origin: Although no specific pharmacokinetic study was conducted to investigate the effects of race on the disposition of aripiprazole, population pharmacokinetic evaluation of ABILIFY MAINTENA showed no evidence of race-related differences on the pharmacokinetics of aripiprazole. Hepatic Insufficiency: In a single-dose trial (15 mg of oral aripiprazole) in patients with varying degrees of liver cirrhosis (Child-Pugh Classes A, B, and C), the AUC of aripiprazole, compared to healthy subjects, increased 31% in mild hepatic impairment, increased 8% in moderate hepatic impairment, and decreased 20% in severe hepatic impairment, but the study included only 3 patients with Class C liver cirrhosis, which is insufficient to draw conclusions on their metabolic capacity. Renal Insufficiency: In patients with severe renal impairment (creatinine clearance <30 mL/min), Cmax of aripiprazole (given in a single oral dose of 15 mg) and dehydro-aripiprazole increased by 36% and 53%, respectively, but AUC was 15% lower for aripiprazole and 7% higher for dehydroaripiprazole. Renal excretion of both unchanged aripiprazole and dehydro-aripiprazole is less than 1% of the dose. No dosage adjustment is required in patients with renal impairment. Smoking: Based on studies utilizing human liver enzymes in vitro, aripiprazole is not a substrate for CYP1A2 and also does not undergo direct glucuronidation. Smoking should, therefore, not have an effect on the pharmacokinetics of aripiprazole. Population pharmacokinetic evaluation of oral aripiprazole has revealed no evidence of clinically relevant effects from smoking on the pharmacokinetics of aripiprazole.
- 11. Storage, Stability, and Disposal
Vial:
Store between 15 and 30 °C. For storage conditions after reconstitution of the medicinal product, see 4.3 Reconstitution. Any unused product or waste material should be disposed of in accordance with local requirements.
Pre-filled dual chamber syringe:
Store between 15 and 30 °C. Do not freeze. Protect the syringe from light by storing in the original package until time of use.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: aripiprazole monohydrate
Chemical name: 7-[4-[4-(2,3-dichlorophenyl)-1-piperazinyl] butoxy]-3,4 dihydrocarbostyril as monohydrate
Molecular formula and molecular mass: C23H27Cl2N3O2.H2O
466.40 g/mol
Structural formula: N N CH2CH2CH2CH2O N H O Cl Cl H2O.
Physicochemical properties: Aripiprazole monohydrate is a white to off white crystalline powder.
Aripiprazole monohydrate is practically insoluble in water. The pKa was determined to be 7.6 (in 20% ethanol solution).
14. Clinical Trials
14.1. Clinical Trials by Indication
The efficacy of ABILIFY MAINTENA in achieving and maintaining symptomatic control and delaying relapse in schizophrenia was established in three randomized, double-blind trials. In addition, the efficacy of ABILIFY MAINTENA in the treatment of patients with schizophrenia was established, in part, on the basis of efficacy data from trials with the oral formulation of aripiprazole.
Schizophrenia
The trial design is summarized below in Table 10:
Table 10: Summary of Patient Demographics for Clinical Trials in Acute Schizophrenia and Maintenance Phase of Schizophrenia
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (Range) | Sex |
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (Range) | Sex |
Acute Schizophrenia Trial (31-12-291) | Phase 3, 12-week, randomized, double-blind, placebo-controlled trial | 400/ 300 mg ABILIFY MAINTENA (with oral aripiprazole 10-20 mg/day for Weeks 1-2) or placebo on days 0, 28, and 56 | ABILIFY MAINTENA (168) Placebo (172) | 42.4 years (range, 18-65 years) | 269 males (79.1%) 71 females (20.9%) |
Maintenance Trial 1 Schizophrenia (31-07-247) | Phase 3, randomized (2:2:1), double-blind, active controlled, parallel arms, with preceding phases to convert (if applicable) and stabilize subjects to daily oral aripiprazole | Conversion Phase (4-6 weeks): oral aripiprazole (5, 10, or 15 mg tablets) 10-30 mg/day. | Conversion Phase: 709 | 41.2 years (range, 18-60 years) | 472 males (66.6%) 237 females (33.4%) |
| Oral Stabilization Phase (8-28 weeks): oral aripiprazole (5, 10, or 15 mg tablets) 10-30 mg/day. | Oral Stabiliza- tion Phase: 842 | 40.8 years (range, 18-60 years) | 518 males: (61.5%) 324 females (39.5%) | ||
| Double-Blind, Active-Controlled Phase (38 weeks), 2:2:1 randomization to double-blind treatment to: 1) ABILIFY MAINTENA 400 mg or 300 mg once monthly, 2) the stabilization dose of oral aripiprazole 10-30 mg/day, or 3) aripiprazole IM depot 50 mg/25 mg. | Double- blind, Active- controlled Phase: 662 | 41.2 years (range, 18-60 years) | 406 males (61.3%) 256 females (38.7%) | ||
Maintenance Trial 2 Schizophrenia (31-07-246) | Phase 3, 52-week, randomized-withdrawal, double-blind, placebo-controlled trial | Conversion Phase (4-6 weeks): oral aripiprazole (5-,10-, 15-mg tablets) 10-30 mg/day | Conversion Phase: 633 | 40.0 years (range, 18-61 years) | 386 males (61.0%) 247 females (39.0%) |
| Oral Stabilization Phase (4-12 weeks): oral aripiprazole (5-,10-, 15-mg tablets) 10-30 mg/day | Oral Stabiliza-tion Phase: 710 | 39.7 years (range, 18-60 years) | 428 males (60.3%) 282 females (39.7%) | ||
| IM Depot Stabilization Phase (12-36 weeks): aripiprazole IM depot (lyophilized powder for injection) 400 mg or 300 mg once monthly with oral aripiprazole 10-20 mg/day continued for Weeks 1- 2 | IM Depot Stabilization Phase: 576 | 39.9 years (range, 18-60 years) | 349 males (60.6%) 227 females (39.4%) | ||
| Double-blind Placebo-controlled Phase (up to 52 weeks): aripiprazole IM depot 400 or 300 mg once monthly or placebo once monthly | Double- blind Placebo- controlled Phase: 403 | 40.6 years (range, 18-61 years) | 241 males (59.8%) 162 females (40.2%) |
Clinical Efficacy in the Acute Phase of Schizophrenia
The efficacy of ABILIFY MAINTENA in adult patients in the acute phase of schizophrenia was established in one short-term (12-week), randomized, double-blind, placebo-controlled trial of acutely relapsed adult patients. In this trial, the primary measure used for assessing psychiatric signs and symptoms was the Positive and Negative Syndrome Scale (PANSS). The primary endpoint was the change from baseline to week 10 in PANSS total score. The key secondary endpoint was the Clinical Global Impression-Severity (CGI-S) assessment at week 10. The inclusion criteria for this short-term trial included adult inpatients who met DSM-IV-TR criteria for schizophrenia. In addition, all patients entering the trial must have experienced an acute psychotic episode as defined by both PANSS Total Score ≥ 80 and a PANSS score of > 4 on each of four specific psychotic symptoms (conceptual disorganization, hallucinatory behaviour, suspiciousness/persecution, unusual thought content) at screening and baseline. Patients had a mean PANSS total score of 103 (range 82 to 144) and a CGI-S score of 5.0 (markedly ill) at entry. In this 12-week study (n=339) comparing ABILIFY MAINTENA (n=167) to placebo (n=172), patients were administered 400 mg ABILIFY MAINTENA or placebo on days 0, 28, and 56. The dose could be adjusted down and up within the range of 400 to 300 mg on a one time basis. (For the first two weeks of the study, patients randomized to ABILIFY MAINTENA also received concomitant oral ABILIFY, 10 to 20 mg/day). ABILIFY MAINTENA was superior to placebo in improving the PANSS total score with early onset and sustained efficacy (week 10 scores of -26.8 vs. -11.7 respectively) with a statistical difference at each measured time point, p=<0.0005 at week 1 and p=<0.0001 for all other time points until study completion. The adjusted mean change in PANSS total score over time (Mixed Model of Repeated Measure MMRM) is demonstrated in Figure 20.
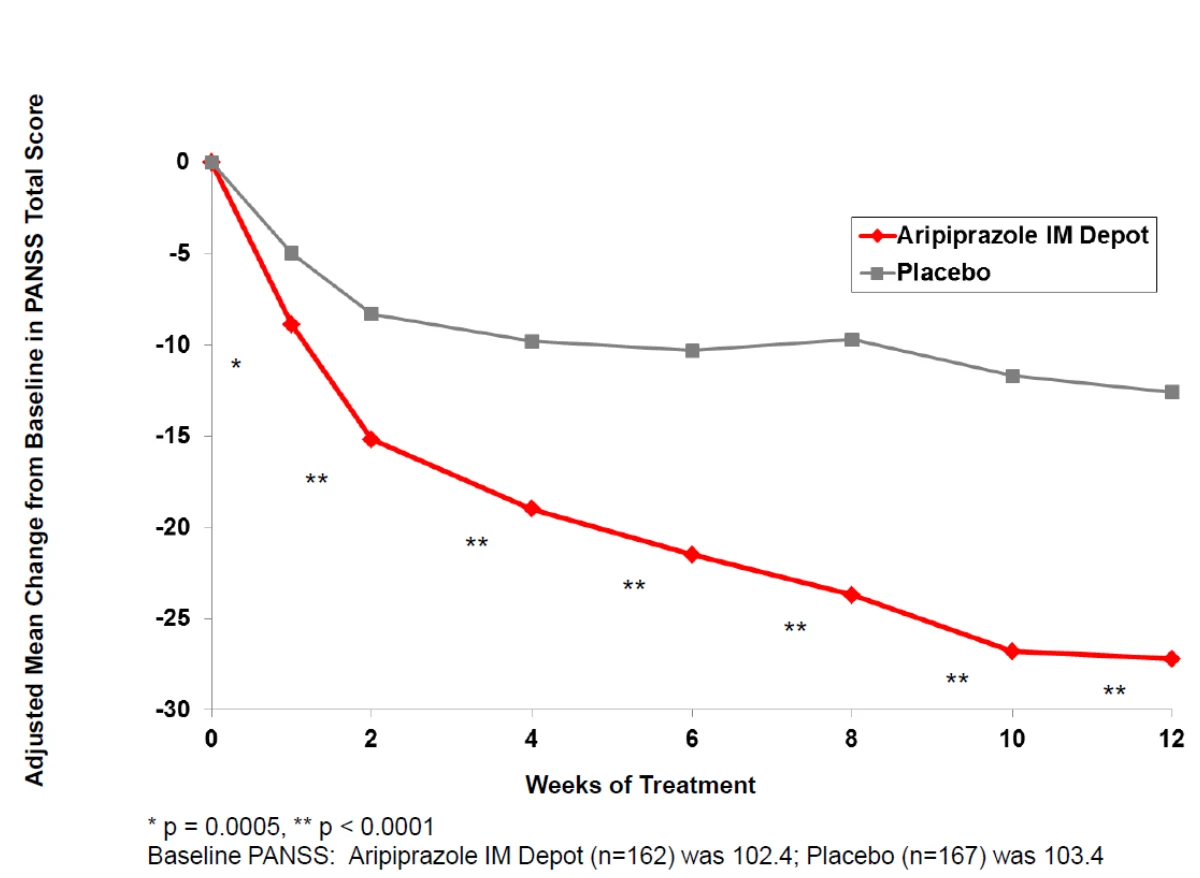
Figure 20: Adjusted Mean Change from Baseline in PANSS Total Score – MMRM
ABILIFY MAINTENA also showed improvement in CGI-S score mean changes from baseline that were statistically significant at all post-baseline timepoints (week 10 scores of -1.4 vs. -0.6 at week 10, ABILIFY MAINTENA vs. placebo, respectively).
Clinical Efficacy in the Maintenance Phase of Schizophrenia
The first trial, Trial 1, was a 38-week, randomized, double-blind, active-controlled trial designed to establish the efficacy, safety, and tolerability of ABILIFY MAINTENA 400 mg/300 mg administered as monthly injections compared to once daily oral aripiprazole tablets 10-30 mg as maintenance treatment in adult patients with schizophrenia as defined by DSM-IV-TR criteria and a history of the illness for at least 3 years prior to screening and with a history of relapse and/or exacerbation of symptoms when they were not receiving antipsychotic treatment.
This trial consisted of a screening phase and 3 treatment phases:
- A conversion Phase (4 to 6 weeks) for all patients to achieve a monotherapy target starting dose of 10 or 15 mg oral aripiprazole. A total of 709 patients entered this phase.
An oral Stabilization Phase (a minimum of 8 weeks and a maximum of 28 weeks in duration) during which patients were stabilized on an oral dose of aripiprazole ranging from 10 mg to 30 mg daily. Stabilization was defined as having all of the following for eight consecutive weeks: an outpatient status, PANSS total score ≤80, CGI-S ≤4 (moderately ill), and CGI-SS score ≤2
- (mildly suicidal) on Part 1 and ≤5 (minimally worsened) on Part 2; and a score of ≤4 on each of the following PANSS items: conceptual disorganization, suspiciousness, hallucinatory behaviour, and unusual thought content. A total of 842 patients entered this phase. The majority of patients who were enrolled in the Oral Stabilization Phase were male (518/842, 61.5%), Caucasian (489/842, 58.1%). The mean age was 40.8 years (range, 18 to 60 years). The mean baseline PANSS total score was 63.8 (range, 30 to 110). The mean baseline CGI-S severity and CGI-SS severity scores were 3.4 and 1.0, respectively.
- Double-blind, Active-controlled Phase.
Six-hundred and sixty-two patients eligible for the 38-week Double-Blind, Active-Controlled Phase were randomly assigned in a 2:2:1 ratio to double-blind treatment to one of 3 treatment groups: 1) ABILIFY MAINTENA 400 mg/300 mg, 2) the stabilization dose of oral aripiprazole 10-30 mg, or 3) aripiprazole IM depot 50 mg/25 mg. The aripiprazole IM depot 50 mg/25 mg dose was included as a low dose aripiprazole group to test assay sensitivity for the non-inferiority design. The overall demographic characteristics for randomized patients were similar to those seen in the previous phases; most patients randomized were male (406/662, 61.3%), Caucasian (387/662, 58.5%); the mean age was 41.2 years (range, 18 to 60 years). Baseline disease severity was comparable across the 3 treatment groups. The mean age at first diagnosis of schizophrenia was 28.2, 26.9, and 26.3 years for the ABILIFY MAINTENA 400 mg/300 mg, oral aripiprazole tablets 10-30 mg, and IM depot 50 mg/25 mg groups, respectively. The mean baseline PANSS total score was 58.0, 56.6, and 56.1 for the ABILIFY MAINTENA 400 mg/300 mg, oral aripiprazole tablets 10-30 mg, and IM depot 50 mg/25 mg groups, respectively. The mean baseline CGI-S was 3.1 in both the ABILIFY MAINTENA 400 mg/300 mg and oral aripiprazole tablets 10-30 mg groups, and 3.0 in the IM depot 50 mg/25 mg group. Mean baseline CGI-SS was 1.0 in all 3 treatment groups. The primary efficacy endpoint, was the estimated proportion of patients experiencing impending relapse by end of Week 26 of the Double-blind, Active-controlled Phase.
Impending relapse was defined as meeting any or all of the following 4 criteria:
- 1)
Clinical Global Impression of Improvement (CGI-I) of ≥ 5 (minimally worse)
AND
- an increase on any of the following individual Positive and Negative Syndrome Scale (PANSS) items (conceptual disorganization, hallucinatory behaviour, suspiciousness, unusual thought content) to a score > 4 with an absolute increase of ≥ 2 on that specific item since randomization OR
- an increase on any of the following individual PANSS items (conceptual disorganization, hallucinatory behaviour, suspiciousness, unusual thought content) to a score > 4 and an absolute increase of ≥ 4 on the combined 4 PANSS items (conceptual disorganization, hallucinatory behaviour, suspiciousness, unusual thought content) since randomization.
- 2) Hospitalization due to worsening of psychotic symptoms (including partial hospitalization programs), but excluding hospitalization for psychosocial reasons
- 3) Clinical Global Impression of Severity of Suicide (CGI-SS) of 4 (severely suicidal) or 5 (attempted suicide) on Part 1 and/or 6 (much worse) or 7 (very much worse) on Part 2
- 4) Violent behaviour resulting in clinically relevant self-injury, injury to another person, or property damage.
The estimated proportion of patients experiencing impending relapse by end of Week 26 for the ABILIFY MAINTENA 400 mg/300 mg group was 7.12%, which was statistically significantly lower than in the aripiprazole IM depot 50 mg/25 mg group (21.80%; p = 0.0006). Thus, superiority of ABILIFY MAINTENA 400 mg/300 mg over the aripiprazole IM depot 50 mg/25 mg was established and the validity of the trial design was confirmed. The proportion of patients who met the stability criteria at endpoint in the Double-blind, Active-controlled Phase was 89.8% (237/264) in the ABILIFY MAINTENA 400 mg/300 mg group compared with 75.2% (97/129) in the aripiprazole IM depot 50 mg/25 mg group.
The Kaplan-Meier curves of the secondary efficacy endpoint time from randomization to impending relapse during the 38-week, double-blind treatment phase for ABILIFY MAINTENA 400 mg/300 mg, oral aripiprazole 10-30mg group, and aripiprazole IM depot 50 mg/25 mg groups are shown in Figure 21. The aripiprazole IM depot 50 mg/25 mg group had a 3.158-fold higher risk of relapse than the ABILIFY MAINTENA 400 mg/300 mg group (95% CI = 1.813, 5.502). As shown below, ABILIFY MAINTENA significantly delayed time to impending relapse.
*ARIP IMD = ABILIFY MAINTENA; ORAL ARIP = oral aripiprazole;
Figure 21: Kaplan-Meier Product Limit Plot for Time to Exacerbation of Psychotic
Symptoms/Impending Relapse*
The second trial, Trial 2, was a 52-week, randomized-withdrawal, double-blind, placebo-controlled trial conducted in adult patients with a current diagnosis of schizophrenia as defined by DSM-IV-TR criteria and a history of the illness for at least 3 years prior to screening and with a history of relapse and/or exacerbation of symptoms when they were not receiving antipsychotic treatment. This trial consisted of a screening phase and 4 treatment phases:
- A 4-6 week open-label, oral conversion phase for patients on antipsychotic medications other than aripiprazole. A total of 633 patients entered this phase.
- An open-label, oral aripiprazole stabilization phase (target dose of 10 mg to 30 mg once daily). A total of 710 patients entered this phase. Patients were 18 to 60 years old (mean 40 years) and 60% were male. The mean PANSS total score was 66 (range 33 to 124). The mean CGI-S score was 3.5 (mildly to moderately ill). Prior to the next phase, stabilization was required. Stabilization was defined as having all of the following for four consecutive weeks: an outpatient status, PANSS total score ≤80, CGI-S ≤4 (moderately ill), and CGI-SS score ≤2 (mildly suicidal) on Part 1 and ≤5 (minimally worsened) on Part 2; and a score of ≤4 on each of the following PANSS items: conceptual disorganization, suspiciousness, hallucinatory behaviour, and unusual thought content.
- A 12-week uncontrolled, single-blind ABILIFY MAINTENA stabilization phase (treatment with 400 mg of ABILIFY MAINTENA given every 4 weeks in conjunction with oral aripiprazole [10 mg to 20 mg/day] for the first 2 weeks). The dose of ABILIFY MAINTENA may have been decreased to 300 mg due to adverse reactions. A total of 576 patients entered this phase. The mean PANSS total score was 59 (range 30 to 80) and the mean CGI-S score was 3.2 (mildly ill). Prior to the next phase, stabilization was required (see above for the definition of stabilization) for 12 consecutive weeks.
- A double-blind, placebo-controlled randomized-withdrawal phase to observe for relapse (defined as in trial 1). A total of 403 patients were randomized 2:1 to the same dose of ABILIFY MAINTENA they were receiving at the end of the stabilization phase, (400 mg or 300 mg administered once every 4 weeks) or placebo. Patients had a mean PANSS total score of 55 (range 31 to 80) and a CGI-S score of 2.9 (mildly ill) at entry. The dose could be adjusted up and down or down and up within the range of 300 to 400 mg on a one time basis.
The trial design included two pre-specified interim analyses for efficacy in order to minimize continued exposure to placebo and the risk of relapse: the first was to occur after accrual of 50% of the 125 targeted impending relapse events (64 events) and the second was to occur after 75% accrual of the events (94 events). A Data Monitoring Committee (DMC) was responsible for ongoing safety monitoring and evaluation of efficacy from the pre-specified interim analyses. Since the first pre-specified interim analysis showed statistically significant superiority of ABILIFY MAINTENA over IM placebo in time to impending relapse, the study was terminated early.
The final efficacy analysis included 403 randomized patients and 80 “exacerbation of psychosis/impending relapse” events. In this analysis, time to impending relapse was significantly delayed with ABILIFY MAINTENA compared with IM placebo (p < 0.0001; log-rank test). Similar results were observed at the interim analysis, with a significantly longer time to impending relapse with ABILIFY MAINTENA compared with placebo (log-rank test, P<.0001 and significantly lower relapse rates with ABILIFY MAINTENA (9.6% n=22/230) than placebo (36.8%; n=42/114; HR=4.72, 95% CI, 2.81-7.94). The Kaplan-Meier curves of the time from randomization to impending relapse during the double-blind treatment phase for ABILIFY MAINTENA and placebo groups are shown in Figure 22. The key secondary efficacy endpoint, proportion of patients meeting the impending relapse criteria, was significantly lower in the ABILIFY MAINTENA 400 mg/300 mg group (interim analysis: 9.6%; final analysis:10.0%) than in the placebo group (interim analysis: 36.8%; final analysis: 39.6%).
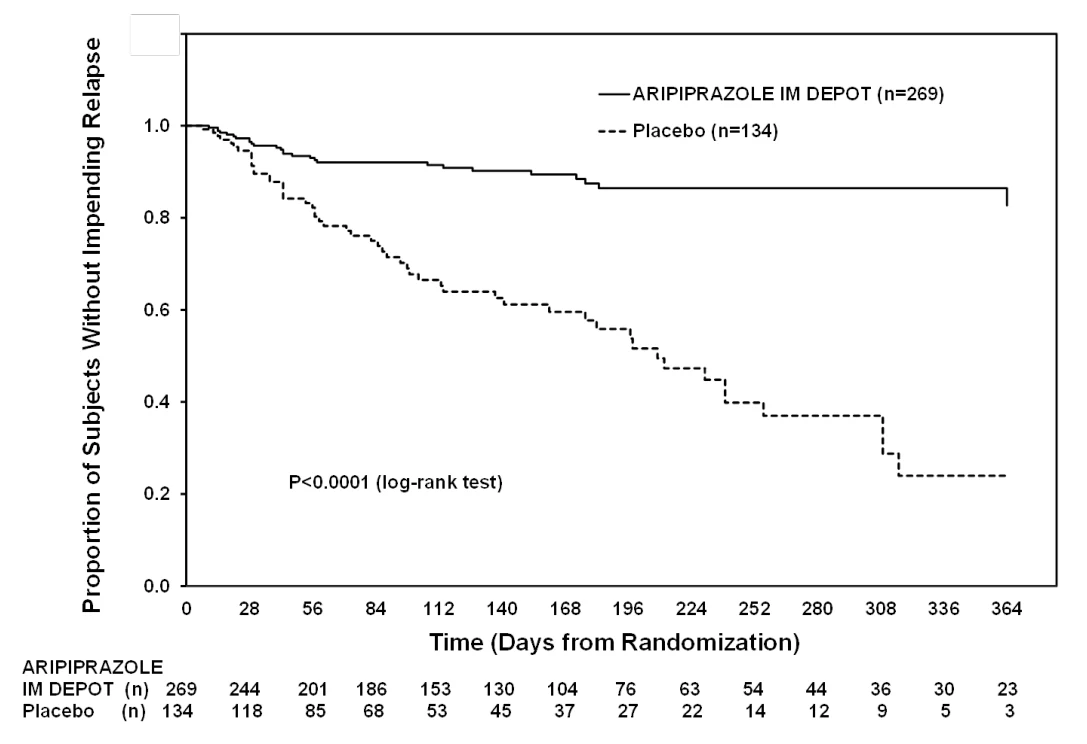
Figure 22: Kaplan-Meier Product Limit Plot for Time to Exacerbation of Psychotic Symptoms/Impending Relapse
Bipolar I Disorder
The efficacy of ABILIFY MAINTENA as maintenance treatment in adults with bipolar I disorder was demonstrated in a 52-week multicenter, randomized, double-blind, placebo-controlled trial of patients with bipolar I disorder who were currently experiencing a manic episode at trial entry. An additional 52-week open label trial was conducted to primarily assess the safety of ABILIFY MAINTENA. In addition, the efficacy of ABILIFY MAINTENA in the treatment of patients with bipolar I disorder was established, in part, on the basis of efficacy data from trials with the oral formulation of aripiprazole.
The trial design is summarized below in Table 11:
Table 11: Summary of Patient Demographics for Clinical Trial in Bipolar Disorder
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (Range) | Sex |
| Bipolar I disorder trial | Phase 3, randomized (1:1), double blind, placebo- controlled, parallel arm, with preceding phases to convert subjects | Conversion Phase (4 to 6 weeks): oral aripiprazole tablets (target dose of 15 mg/day) | Conversion Phase: 466 | 41.9 years (range, 18-66 years) | 198 males (42.5%) 268 females (57.5%) |
| Oral Stabilization Phase (2-8 weeks): oral aripiprazole tablets (target dose of 15- 30 mg/day) | Oral Stabiliza- tion Phase: 632 | 40.7 years (range, 18-66 years) | 255 males: (40.3%) 377 females |
Clinical Efficacy in Maintenance Treatment of Bipolar I Disorder
The safety and efficacy of ABILIFY MAINTENA as maintenance treatment in adults with bipolar I disorder aged 18 to 65 years was demonstrated in a 52-week multicenter, randomized, double-blind, placebo-controlled trial (Trial 31-08-250) of patients who met DSM-IV-TR criteria for bipolar I disorder and who were currently experiencing a manic episode at trial entry.
This trial consisted of a screening phase and 4 treatment phases:
- An oral conversion phase (4 to 6 weeks) for all patients to achieve a monotherapy target starting dose of 15 mg/day oral aripiprazole. A total of 466 patients entered this phase.
- An oral stabilization phase (a minimum of 2 weeks and a maximum of 8 weeks in duration) during which patients were stabilized on an oral dose of aripiprazole ranging from 15 mg to 30 mg daily. Stabilization was defined as having all of the following stability criteria at one biweekly visit in order to proceed to ABILIFY MAINTENA stabilization phase: outpatient status, YMRS total score ≤ 12, MADRS total score ≤ 12, no active suicidality; with active suicidality defined as a score of 4 or more on the MADRS item 10 OR an answer of “yes” on question 4 or 5 on the Columbia Suicide Severity Rating Scale (C-SSRS). A total of 632 patients entered this phase of which 265 patients entered the oral stabilization phase directly.
- ABILIFY MAINTENA Stabilization Phase (a minimum of 12 weeks and a maximum of 28 weeks in duration) during which patients were stabilized on ABILIFY MAINTENA 400 mg or 300 mg, as dictated by tolerability. Oral dosing with aripiprazole continued for the first 2 weeks following the injection to maintain therapeutic plasma concentrations. Stabilization was defined as having all of the following for eight consecutive weeks: an outpatient status, YMRS total score ≤ 12, MADRS total score ≤ 12, no active suicidality; with active suicidality defined as a score of 4
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (Range) | Sex | ||||||
| to daily oral aripiprazole tablets (if applicable), stabilize on daily oral aripiprazole tablets, and then stabilize on single- blind aripiprazole IM depot | (59.7%) | ||||||||||
| IM Depot Stabilization Phase (12-28 weeks): single-blind aripiprazole IM depot 400 mg or 300 mg once monthly with oral aripiprazole tablets 10 or 15 mg/day continued for Weeks 1-2; single decrease to 300 mg permitted, as was single return to 400 mg, if required. | IM Depot Stabilization Phase: 425 | 40.3 years (range, 18-66 years) | 169 males (39.8%) 256 females (60.2%) | ||||||||
| Double-blind Placebo-controlled Phase (52 weeks): 1:1 randomization to aripiprazole IM depot (400 or 300 mg) or placebo once monthly | Double-blind Placebo-controlled Phase: 266 | 40.6 years (range, 19-66 years) | 113 males (42.5%) 153 females (57.5%) | ||||||||
- or more on the MADRS item 10 OR an answer of “yes” on question 4 or 5 on the Columbia Suicide Severity Rating Scale (C-SSRS). A total of 425 patients entered this phase. The mean baseline YMRS total score was 5.8 (range, 0 to 28). The mean baseline MADRS total score was 3.7 (range, 0 to 28). The mean baseline CGI-BP-S overall score was 2.1 (range, 1 to 5). Patients who demonstrated stability for 8 consecutive weeks were randomized into the double-blind, placebo- controlled treatment phase.
- A randomized, double-blind, placebo-controlled phase (52 weeks). Two hundred sixty-six (266) patients eligible for the 52-week double-blind, placebo-controlled phase were randomly assigned in a 1:1 ratio to double-blind treatment with either the last stabilization dose of ABILIFY MAINTENA from the previous phase or placebo. During this phase, a single decrease to ABILIFYMAINTENA 300 mg was permitted for tolerability, as was a single return to the original 400 mg dose if required. The mean baseline YMRS total score was 2.9, and 2.6 for the ABILIFY MAINTENA 400 mg/300 mg and placebo groups, respectively. The mean baseline MADRS total score was 3.0 and 2.4 for the ABILIFY MAINTENA 400 mg/300 mg and placebo groups, respectively. The mean baseline CGI-BP-S score was 1.5 and 1.4 for the ABILIFY MAINTENA 400 mg/300 mg and placebo groups, respectively.
The primary efficacy endpoint of this trial was the time from randomization to recurrence of any mood episode during the double-blind, placebo-controlled phase. The time to recurrence of any mood episode was significantly longer in patients randomized to the ABILIFY MAINTENA group compared to placebo-treated patients. A total of 103 mood events were observed during the double-blind treatment phase: 35 occurred during ABILIFY MAINTENA treatment and 68 occurred during placebo treatment (26.5% vs 51.1%, p < 0.0001). The hazard ratio from the Cox proportional hazard model for the ABILIFY MAINTENA to placebo comparison was 0.451 (95% CI = 0.299, 0.678), patients in the ABILIFY MAINTENA group had less than half the risk of experiencing recurrence of any mood episode compared with patients in the placebo group. Thus, superiority of ABILIFY MAINTENA over placebo was established. The analysis of the primary efficacy endpoint is shown in the Kaplan-Meier curves below (Figure 23).
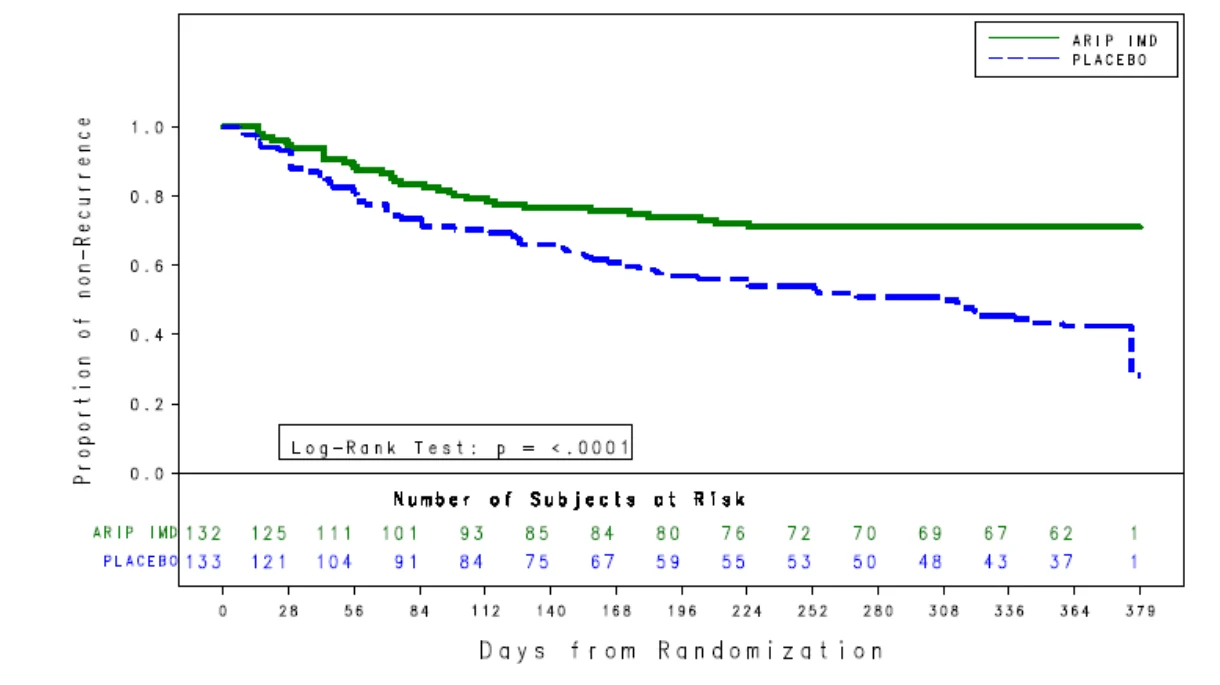
n = number of patients at risk of recurrence
ARIP IMD = Aripiprazole IM depot (ABILIFY MAINTENA)
Figure 23: Kaplan-Meier Curves of Time to Recurrence for any Mood Episode
Secondary and other efficacy endpoints were generally supportive of the primary efficacy outcome. ABILIFY MAINTENA as maintenance treatment in adults with bipolar I disorder was assessed in a 52-week multicentre, open-label trial (n=464, Trial 31-08-252). Safety and tolerability were supportive of the results observed in the double-blind, placebo-controlled study.
16. Non-Clinical Toxicology
General toxicology
Intramuscular Aripiprazole
The toxicological profile for aripiprazole administered to experimental animals by intramuscular injection is generally similar to that seen following oral administration at comparable plasma levels of the drug. With intramuscular injection, however, injection-site tissue reactions were observed that consisted of localized inflammation, swelling, scabbing and foreign-body reactions to deposited drug. These effects gradually resolved with discontinuation of dosing. In dogs, repeated intramuscular dosing of the two-month aripiprazole prolonged release injectable suspension administered once every 4 weeks over a period of 52 weeks produced no clinical evidence of significant local irritation, and resulted in a slight foreign-body type of localized granulomatous inflammatory reaction to deposited drug at the injection site.
Acute Toxicity
The acute oral toxicity of aripiprazole was determined in rats and monkeys. The estimated median lethal oral dose in male and female rats was 953 and 705 mg/kg, respectively, and in monkeys was greater than 2000 mg/kg for both sexes. Clinical signs consistent with pharmacologically mediated central nervous (CNS) depression and extrapyramidal side effects were noted in both species. In rats, clinical signs included decreased spontaneous motor activity, crouching, prone position, ataxia, tremors, convulsions, straub tail, catalepsy, ptosis, and coldness to touch. In monkeys, principal drug-related effects included impaired motor activity, hyporeactivity to external stimuli, tremors, catalepsy, closed eyes, crouching, and prone and/or lateral position.
Short- and Long-Term Toxicity
The repeat-dose oral toxicity of aripiprazole in rats was evaluated in a 13-week study (2, 6, or 20 mg/kg/day), a 52-week study (1, 3, or 10 mg/kg/day), a 4-week study (60 or 100 mg/kg/day), and a 26-week (6 month) study (10, 30, or 60 mg/kg/day). The repeat-oral dose toxicity of aripiprazole in monkeys was evaluated in a 13-week study (0.5, 1, 5, or 25 mg/kg/day), a 52-week study (0.5, 5, or 25 mg/kg/day), and a 39-week study (25, 50, or 75 mg/kg/day). Aripiprazole did not cause life-threatening toxicity when given to rats at doses up to 60 mg/kg/day for 6 months or to monkeys at doses up to 75 mg/kg/day for 9 months.
CNS-related clinical signs in rats were postdose hypoactivity and ptosis and predose hyperactivity at 30 and 60 mg/kg/day in the 26-week study. Morphological changes reflective of exaggerated pharmacology or considered secondary to drug-related increases (females) or decreases (males) in serum prolactin levels were observed microscopically in the pituitary, ovaries, female reproductive tract, mammary gland, epididymides, and/or testes. These changes included atrophy of the pars intermedia of the pituitary gland, mammary gland hyperplasia (females) or atrophy (males), vaginal mucification, persistent ovarian corpora lutea, uterine atrophy, minimal to moderate testicular atrophy, and increased numbers of exfoliated germinal epithelial cells in epididymides. Drug-related direct target organ changes were limited to dose-related increased incidence and/or severity of alveolar macrophages (pulmonary histiocytosis) in lungs at all doses after 4 and 26 weeks, and minimally increased lipofuscin pigment accumulation in the adrenal cortex at 30 and 60 mg/kg/day and in the ovaries at 60 mg/kg/day after 26 weeks. In addition, an increased incidence of inflammation of the prostatic ampullary gland was seen at 30 and 60 mg/kg/day after 26 weeks. All pituitary, reproductive organ and mammary gland changes were reversible. The pulmonary histiocytosis was partially reversible. In the 52-week toxicity study in rats, which was conducted at lower doses than given in the 26-week toxicity study, NOAEL for effects was established at 1 (female) or 3 mg/kg/day (male). In monkeys, the principal pharmacologically-mediated CNS signs (e.g., impaired motor activity, hyporeactivity, tremors, catalepsy, and abnormal posture) were most prominent during the first 1 to 2 weeks of dosing, were generally mild and transient at 5 mg/kg/day, and decreased in incidence and severity with continued dosing at 25 mg/kg/day. Similar CNS-related clinical signs were noted in the 39-week toxicity study primarily during the first 4 weeks at 25 mg/kg/day and throughout the dosing period at 50 and 75 mg/kg/day. No life-threatening clinical signs were occurred at doses up to 75 mg/kg/day/day for 39 weeks or 25 mg/kg/day for 52 weeks. Gallsand (muddy substance, granular material) in bile was noted at 25 mg/kg/day after 13 weeks, and dose-related incidence of gallsand or gallstones (calculi) were observed in gallbladder at ≥ 25 mg/kg/day in the 39- and 52-week studies. Gallsand at 25 and 125 mg/kg/day and a gallstone at 125 mg/kg/day were also seen in the 4-week toxicity study. Minimal focal hepatolithiasis was observed at in the subscapular parenchyma (proximal to gallbladder) of liver in 2 monkeys given 50 mg/kg/day and in 1 monkey given 75 mg/kg/day for 39 weeks. There were no correlative alterations in liver functions tests. The gallsand and gallstones were considered a consequence of concentration and precipitation of sulfate conjugates, which, due to their limited solubility, precipitate out in the bile, or hydroxy metabolites of aripiprazole in the terminal biliary tree and gallbladder. No other target organs of toxicity were identified in monkeys. There was no evidence of other target organ toxicity at any dose level. In the 13-week toxicity study, drug-related changes at 25 mg/kg/day were reversible or improved during the 4-week postdose period. In the 52-week toxicity study in monkeys, which was conducted at lower doses than given in the 39-week toxicity study, the NOAEL for effects was established at 0.5 mg/kg/day. Genotoxicity The mutagenic potential of aripiprazole was tested in the in vitro bacterial reverse-mutation assay, the in vitro bacterial DNA repair assay, the in vitro forward gene mutation assay in mouse lymphoma cells, the in vitro chromosomal aberration assay in Chinese hamster lung (CHL) cells, the in vivo micronucleus assay in mice, and the unscheduled DNA synthesis assay in rats. Aripiprazole and a metabolite (2,3-DCPP) were clastogenic in the in vitro chromosomal aberration assay in CHL cells with and without metabolic activation. The metabolite, 2,3-DCPP, produced increases in numerical aberrations in the in vitro assay in CHL cells in the absence of metabolic activation. A positive response was obtained in the in vivo micronucleus assay in mice; however, the response was due to a mechanism considered not relevant to humans. Carcinogenicity Lifetime carcinogenicity studies were conducted in ICR mice and in Sprague-Dawley (SD) and F344 rats. Oral aripiprazole was administered for 2 years in the diet at doses of 1, 3, 10, and 30 mg/kg/day to ICR mice and 1, 3, and 10 mg/kg/day to F344 rats (0.2 to 5 and 0.3 to 3 times the MRHD based on mg/m2, respectively). In addition, SD rats were dosed orally for 2 years at 10, 20, 40, and 60 mg/kg/day (3 to 19 times the MRHD based on mg/m2). Aripiprazole did not induce tumors in male mice or rats. In female mice, the incidences of pituitary gland adenomas, mammary gland adenocarcinomas and adenoacanthomas were increased at dietary doses of 3 to 30 mg/kg/day (0.1 to 0.9 times human exposure at MRHD based on AUC). In female rats, the incidence of mammary gland fibroadenomas was increased at a dietary dose of 10 mg/kg/day (0.1 times human exposure at MRHD based on AUC) and the incidences of adrenocortical carcinomas and combined adrenocortical adenomas/carcinomas were increased at an oral dose of 60 mg/kg/day (10 times human exposure at MRHD based on AUC). Proliferative changes in the pituitary and mammary gland of rodents have been observed following chronic administration of other antipsychotic agents and are considered prolactin mediated. Serum prolactin was not measured in the aripiprazole carcinogenicity studies. However, increases in serum prolactin levels were observed in female mice in a 13-week dietary study at the doses associated with mammary gland and pituitary tumors. Serum prolactin was not increased in female rats in 4- and 13-week dietary studies at the dose associated with mammary gland tumors. The relevance for human risk of the findings of prolactin-mediated endocrine tumors in rodents is unknown. Reproductive and developmental toxicology In animal studies, aripiprazole demonstrated developmental toxicity, including possible teratogenic effects in rats and rabbits. Pregnant rats were treated with oral doses of 3, 10, and 30 mg/kg/day (1, 3, and 10 times the maximum recommended human dose [MRHD] on a mg/m2 basis) of aripiprazole during the period of organogenesis. Gestation was slightly prolonged at 30 mg/kg. Treatment caused a slight delay in fetal development, as evidenced by decreased fetal weight (30 mg/kg), undescended testes (30 mg/kg), and delayed skeletal ossification (10 and 30 mg/kg). There were no adverse effects on embryofetal or pup survival. Delivered offspring had decreased bodyweights (10 and 30 mg/kg), and increased incidences of hepatodiaphragmatic nodules and diaphragmatic hernia at 30 mg/kg (the other dose groups were not examined for these findings). A low incidence of diaphragmatic hernia was also seen in the fetuses exposed to 30 mg/kg. Postnatally, delayed vaginal opening was seen at 10 and 30 mg/kg and impaired reproductive performance (decreased fertility rate, corpora lutea, implants, and live fetuses and increased post implantation loss, likely mediated through effects on female offspring) was seen at 30 mg/kg. Some maternal toxicity was seen at 30 mg/kg; however, there was no evidence to suggest that these developmental effects were secondary to maternal toxicity. In pregnant rats receiving aripiprazole injection intravenously (3, 9, and 27 mg/kg/day) during the period of organogenesis, decreased fetal weight and delayed skeletal ossification were seen at the highest dose, which also caused maternal toxicity. Pregnant rabbits were treated with oral doses of 10, 30, and 100 mg/kg/day (2, 3, and 11 times human exposure at MRHD based on AUC) of aripiprazole during the period of organogenesis. Decreased maternal food consumption and increased abortions were seen at 100 mg/kg. Treatment caused increased fetal mortality (100 mg/kg), decreased fetal weight (30 and 100 mg/kg), increased incidence of a skeletal abnormality (fused sternebrae at 30 and 100 mg/kg), and minor skeletal variations (100 mg/kg). In pregnant rabbits receiving aripiprazole injection intravenously (3, 10, and 30 mg/kg/day) during the period of organogenesis, the highest dose, which caused pronounced maternal toxicity, resulted in decreased fetal weight, increased fetal abnormalities (primarily skeletal), and decreased fetal skeletal ossification. The fetal no-effect dose was 10 mg/kg, which produced 5 times the human exposure at the MRHD based on AUC. In a study in which rats were treated with oral doses of 3, 10, and 30 mg/kg/day (1, 3, and 10 times the MRHD on a mg/m2 basis) of aripiprazole perinatally and postnatally (from day 17 of gestation through day 21 postpartum), slight maternal toxicity and slightly prolonged gestation were seen at 30 mg/kg. An increase in stillbirths and decreases in pup weight (persisting into adulthood) and survival were seen at this dose. In rats receiving aripiprazole injection intravenously (3, 8, and 20 mg/kg/day) from day 6 of gestation through day 20 postpartum, an increase in stillbirths was seen at 8 and 20 mg/kg, and decreases in early postnatal pup weights and survival were seen at 20 mg/kg. These doses produced some maternal toxicity. There were no effects on postnatal behavioural and reproductive development. Impairment of Fertility Female rats were treated with oral doses of 2, 6, and 20 mg/kg/day (0.6, 2, and 6 times the MRHD on a mg/m2 basis) of aripiprazole from 2 weeks prior to mating through day 7 of gestation. Estrus cycle irregularities and increased corpora lutea were seen at all doses, but no impairment of fertility was seen. Increased pre-implantation loss was seen at 6 and 20 mg/kg and decreased fetal weight was seen at 20 mg/kg. Male rats were treated with oral doses of 20, 40, and 60 mg/kg/day (6, 13, and 19 times the MRHD on a mg/m2 basis) of aripiprazole from 9 weeks prior to mating through mating. Disturbances in spermatogenesis were seen at 60 mg/kg and prostate atrophy was seen at 40 and 60 mg/kg, but no impairment of fertility was seen.
Special toxicology
Adrenocortical Changes in Rats
A series of investigative studies were conducted in rats to determine the mechanism for the aripiprazole-related adrenocortical changes after sub-chronic and chronic dosing. The data from these studies supported the conclusion that the female rat-specific adrenocortical tumorigenic response at 60 mg/kg/day in the oral carcinogenicity study was secondary to aripiprazole-related adrenocortical cytotoxicity and consequent increased cell proliferation. The female specificity of the adrenocortical tumorigenic response was considered a consequence of the earlier onset and greater severity of the adrenocortical cytotoxic changes. The adrenocortical cytotoxic and tumorigenic effects have no established clinical relevance since they occurred at a dose 10 times human exposure at the MRHD based on AUC. Retinal Degeneration in Rats Aripiprazole produced retinal degeneration in albino Sprague-Dawley (SD) rats in a 26-week chronic toxicity study at a dose of 60 mg/kg and in a 2-year carcinogenicity study at doses of 40 and 60 mg/kg. The 40 and 60 mg/kg doses are 7 to 10 times human exposure at the MRHD based on AUC. In a subsequent 18-month investigative study in albino SD and pigmented Long-Evans (LE) rats administered 60 mg/kg/day aripiprazole, pharmacologically mediated hyperactivity occurred in both rat strains early in the study predisposing the animals to increased light exposure. Time-dependent retinal degeneration with electroretinographic and morphologic features consistent with spontaneous light-induced retinal degeneration was observed in albino SD rats, whereas there was no evidence of light-induced retinal injury in pigmented LE rats at any timepoint despite comparable systemic exposures to aripiprazole. This was due to the photoprotective effect of ocular melanin pigment in LE rats. Therefore, the retinal degeneration observed in albino SD rats after chronic dosing at high doses of aripiprazole was considered to be a consequence of drug-related, pharmacologically mediated hyperactivity during the animal room light phase, resulting in increased light exposure rather than a direct drug effect on the retina. Light-induced retinal degeneration in albino SD rats has no established clinical relevance.