


Product Monograph - Rexulti (Otsuka Pharmaceutical, 0.25 mg, ..., 4 mg)
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS | 01/2024 |
|---|---|
| 1 INDICATIONS, 1.2 Geriatrics | 01/2024 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, 4.2.1 Discontinuing Treatment | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | 01/2024 |
| 7 WARNINGS AND PRECAUTIONS | 01/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 01/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 5
2 CONTRAINDICATIONS ................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................ 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 6
4.2.1 Discontinuing Treatment ...................................................................................... 8
4.4 Administration .......................................................................................................... 8
4.5 Missed Dose ............................................................................................................ 8
5 OVERDOSAGE ................................................................................................................ 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 9
7 WARNINGS AND PRECAUTIONS .................................................................................. 9
General ........................................................................................................................... 10
Cardiovascular ................................................................................................................ 10
Dependence/Tolerance ................................................................................................... 11
Driving and Operating Machinery .................................................................................... 12
Endocrine and Metabolism .............................................................................................. 12
Genitourinary ................................................................................................................... 13
Hematologic .................................................................................................................... 13
Immune ........................................................................................................................... 14
Monitoring and Laboratory Tests .................................................................................... 14
Neurologic ....................................................................................................................... 14
Psychiatric ....................................................................................................................... 16
Skin ................................................................................................................................. 16
7.1 Special Populations ............................................................................................... 16
7.1.1 Pregnant Women ............................................................................................... 16
7.1.2 Breast-feeding ................................................................................................... 17
7.1.3 Pediatrics ........................................................................................................... 17
7.1.4 Geriatrics ........................................................................................................... 17
8 ADVERSE REACTIONS ................................................................................................. 19
8.2 Clinical Trial Adverse Reactions ............................................................................ 19
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 31
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 32
8.5 Post-Market Adverse Reactions ............................................................................ 41
9 DRUG INTERACTIONS .................................................................................................. 41
9.2 Drug Interactions Overview ................................................................................... 41
9.3 Drug-Behavioural Interactions ............................................................................... 41
9.4 Drug-Drug Interactions .......................................................................................... 41
9.5 Drug-Food Interactions .......................................................................................... 44
9.6 Drug-Herb Interactions .......................................................................................... 44
9.7 Drug-Laboratory Test Interactions ......................................................................... 44
10 CLINICAL PHARMACOLOGY ....................................................................................... 44
10.1 Mechanism of Action ......................................................................................... 44
10.2 Pharmacodynamics ........................................................................................... 44
10.3 Pharmacokinetics .............................................................................................. 45
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 47
12 SPECIAL HANDLING INSTRUCTIONS ......................................................................... 47
PART II: SCIENTIFIC INFORMATION ....................................................................................... 48
13 PHARMACEUTICAL INFORMATION ............................................................................ 48
14 CLINICAL TRIALS ......................................................................................................... 48
14.1 Clinical Trials by Indication ................................................................................ 48
Schizophrenia ................................................................................................................. 48
Adjunctive Treatment in Major Depressive Disorder (MDD) ........................................... 50
Agitation Associated with Alzheimer’s Dementia (AAD).................................................. 52
15 MICROBIOLOGY ............................................................................................................ 54
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 54
PATIENT MEDICATION INFORMATION .................................................................................. 57
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
REXULTI (brexpiprazole) is indicated for:
- treatment of schizophrenia in adults. In clinical trials, REXULTI was found to significantly improve both positive and negative symptoms.
- use as an adjunct to antidepressants for the treatment of major depressive disorder (MDD) in adult patients with an inadequate response to prior antidepressant treatments during the current episode (see 14.1 Clinical Trials by Indication, Adjunctive Treatment in Major Depressive Disorder (MDD).
- symptomatic management of agitation associated with Alzheimer’s dementia (AAD) in patients with aggressive behaviour, unresponsive to non-pharmacological approaches.
When considering the use of REXULTI as adjunctive treatment in MDD, clinicians must take into account the safety concerns associated with antipsychotic drugs, a class of drugs to which REXULTI belongs. Safety concerns of this class include: weight gain; hyperlipidemia; hyperglycaemia; tardive dyskinesia; and neuroleptic malignant syndrome (see 7 WARNINGS AND PRECAUTIONS, 8 ADVERSE REACTIONS). REXULTI should only be prescribed in patients with MDD by clinicians who are aware of the importance and are experienced in the early detection and management of the safety issues associated with this class of drugs.
The efficacy and safety of REXULTI in the adjunctive treatment of MDD were demonstrated in 6-week, double-blind, placebo-controlled trials in adult patients. Therefore, the required length of adjunctive treatment with REXULTI is not known. When prescribed as an adjunct to antidepressants in the treatment of MDD, REXULTI should be used for the shortest period of time that is clinically indicated (see 14.1 Clinical Trials by Indication, Adjunctive Treatment in Major Depressive Disorder (MDD); 4.2 Recommended Dose and Dosage Adjustment, Adjunctive Treatment in Major Depressive Disorder (MDD)).
Clinical trials evaluating REXULTI in MDD did not include REXULTI monotherapy treatment arms. It is, therefore, not known whether efficacy in adjunct treatment is due to REXULTI alone or from combined treatment with an antidepressant.
REXULTI is not indicated as an as needed (prn) treatment for AAD. It may take up to six to eight weeks after REXULTI initiation to demonstrate significant clinical efficacy (see 14.1 Clinical Trials by Indication, Agitation Associated with Alzheimer’s Dementia (AAD)). The efficacy and safety of REXULTI in the treatment of AAD were demonstrated in two 12-week, randomized, double-blind, placebo-controlled, fixed-dose trials in adult patients. When considering the use of REXULTI for the treatment of AAD, clinicians are advised to assess the risks and benefits of the use of REXULTI in elderly patients with AAD keeping in mind the increased risk of mortality in this patient population treated with antipsychotics (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7.1.4 Geriatrics) and the risk predictors for stroke or existing cardiovascular comorbidities.
1.1 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of REXULTI have not been established in patients less than 18 years of age. REXULTI is not indicated in pediatric patients and its use is not recommended in this population (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (> 65 years of age): The safety and efficacy of REXULTI have not been systematically evaluated in schizophrenia or MDD patients 65 years of age or older, or in AAD patients 90 years of age or older. Caution should be used when treating geriatric patients (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7.1.4 Geriatrics and 10 CLINICAL PHARMACOLOGY).
2 CONTRAINDICATIONS
REXULTI is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING. (See also 7 WARNINGS AND PRECAUTIONS, Immune, and 8.5 Post-Market Adverse Reactions).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- REXULTI is taken orally, once daily with or without food (see 10 CLINICAL PHARMACOLOGY).
- Dosage increases are based on clinical response and tolerability.
- Dosage should be maintained at the lowest effective level and patients should be periodically reassessed to determine continued need and appropriate dosage for treatment.
- Patients should have baseline and periodic monitoring of blood glucose, fasting lipid profile and body weight.
- It is recommended that patients have their complete blood count (CBC), white blood cell (WBC) and differential counts prior to starting REXULTI and then periodically throughout treatment as neutropenia, granulocytopenia and agranulocytosis have been reported during antipsychotic use.
Serious Warnings and Precautions
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA
Increased Mortality in Elderly Patients with Dementia
Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of thirteen placebo-controlled trials with various atypical antipsychotics (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature (see 7.1.4 Geriatrics).
4.2 Recommended Dose and Dosage Adjustment
Table 1: Dose and dose adjustment
| Indication | Starting Dose | Recommended Target Dose | Maximum Dose |
|---|---|---|---|
| Schizophrenia | 1 mg/day | 2-4 mg/day | 4 mg/day |
| Adjunctive Treatment in Major Depressive Disorder (MDD) | 0.5 mg/day or 1 mg/day | 2 mg/day | 2 mg/day |
| Agitation Associated with Alzheimer’s Dementia (AAD) | 0.5 mg/day | 2 mg/day | 3 mg/day |
Schizophrenia
The recommended starting dosage for REXULTI is 1 mg once daily on Days 1 to 4.
The recommended target REXULTI dosage is 2 mg to 4 mg once daily. In short-term fixed-dose clinical trials, the dose was titrated to 2 mg once daily on Day 5 through Day 7, then to 4 mg on Day 8. The maximum recommended daily dosage is 4 mg.
Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability.
Adjunctive Treatment in Major Depressive Disorder (MDD)
The dose range of 1 to 3 mg/day was evaluated as adjunctive treatment in clinical trials. No additional benefit was demonstrated at doses greater than 2 mg/day (see 14.1 Clinical Trials by Indication, Adjunctive Treatment in Major Depressive Disorder (MDD)).
The required length of adjunctive treatment with REXULTI is not known. When prescribed as an adjunct to antidepressants in the treatment of MDD, REXULTI should be used for the shortest period of time that is clinically indicated (see 14.1 Clinical Trials by Indication, Adjunctive Treatment in Major Depressive Disorder (MDD)).
The recommended starting dose for REXULTI as adjunctive treatment is 0.5 mg or 1 mg once daily.
Titrate to 1 mg once daily, then up to the recommended target dosage of 2 mg once daily. Dosage increases should occur at weekly intervals based on the patient’s clinical response and tolerability. The maximum recommended dose is 2 mg once daily.
Agitation Associated with Alzheimer’s Dementia (AAD)
Physicians are advised to assess the risks and benefits of the use of REXULTI in elderly patients with AAD, taking into account risk predictors for stroke or existing cardiovascular comorbidities in the individual patient (see 1 INDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, and 7.1.4 Geriatrics).
Discontinuation should be considered if signs and symptoms of cerebrovascular adverse events occur.
The recommended starting dose for REXULTI is 0.5 mg once daily on Days 1 to 7.
Titrate to 1 mg once daily on Days 8 through 14, and to 2 mg once daily on Day 15. The recommended target dose is 2 mg once daily. After at least 14 days at 2 mg once daily, the dose can be increased to the maximum recommended dose of 3 mg daily, if clinically warranted.
The maximum recommended dose is 3 mg daily. To minimize the risk of adverse events, the lowest effective dose should be used.
Hepatic Impairment: For patients with moderate to severe hepatic impairment (Child-Pugh score ≥7), the maximum recommended dosage is 3 mg once daily for patients with schizophrenia, 1.25 mg once daily for patients with MDD, and 2 mg once daily for patients with AAD.
Renal Impairment: For patients with moderate, severe or end-stage renal impairment (creatinine clearance CLcr<60 mL/minute), the maximum recommended dosage is 3 mg once daily for patients with schizophrenia, 1.25 mg once daily for patients with MDD, and 2 mg once daily for patients with AAD.
CYP isozymes: Dosage adjustments are recommended in patients who are known cytochrome P450 (CYP) 2D6 poor metabolizers and in patients taking concomitant CYP3A4 inhibitors or CYP2D6 inhibitors or strong CYP3A4 inducers (see Table 2). If the co-administered drug is discontinued, adjust the REXULTI dosage to its original level. If the co-administered CYP3A4 inducer is discontinued, reduce the REXULTI dosage to the original level over 1 to 2 weeks.
Table 2: Dosage Adjustments of REXULTI for CYP2D6 Poor Metabolizers and for Concomitant Use with CYP3A4 and CYP2D6 Inhibitors and/or CYP3A4 Inducers
| Factors | Adjusted REXULTI Dosage |
|---|---|
| CYP2D6 Poor Metabolizers | |
| Known CYP2D6 poor metabolizers | Administer half of the usual dose |
| Known CYP2D6 poor metabolizers taking strong/moderate CYP3A4 inhibitors | Administer a quarter of the usual dose |
| Patients Taking CYP2D6 Inhibitors and/or CYP3A4 Inhibitors | |
| Strong CYP2D6 inhibitors* | Administer half of the usual dose |
| Strong CYP3A4 inhibitors | Administer half of the usual dose |
| Strong/moderate CYP2D6 inhibitors with strong/moderate CYP3A4 inhibitors | Administer a quarter of the usual dose |
| Patients Taking CYP3A4 Inducers | |
| Strong CYP3A4 inducers | Double usual dose over 1 to 2 weeks |
*In clinical trials examining the adjunctive use of REXULTI in the treatment of MDD, dosage was not adjusted for strong CYP2D6 inhibitors (e.g., paroxetine, fluoxetine). Thus, CYP considerations are already factored into general dosing recommendations and REXULTI may be administered without dosage adjustment in patients with MDD.
Geriatrics: The safety and efficacy of REXULTI in schizophrenia and MDD patients 65 years of age or older, or in AAD patients 90 years of age or older, have not been established. Caution should be used when treating geriatric patients (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7.1.4 Geriatrics and 10 CLINICAL PHARMACOLOGY).
Pediatrics: The safety and efficacy of REXULTI have not been established in patients less than 18 years of age. REXULTI is not indicated in pediatric patients and its use is not recommended in this population (see 7.1.3 Pediatrics).
4.2.1 Discontinuing Treatment
No specific measures need to be taken to reduce REXULTI dose at the end of the treatment. However, when discontinuing REXULTI, the impact of the elimination half-life of REXULTI (terminal elimination half-life of 91.4 hours) should be considered when drugs that might interact with REXULTI are prescribed (see 9 DRUG INTERACTIONS and 10.3 Pharmacokinetics, Elimination).
4.4 Administration
REXULTI may be given once daily, with or without food.
Switching from Other Antipsychotics
There are no systematically collected data to specifically address switching patients with schizophrenia, MDD or AAD from other antipsychotics to REXULTI or concerning concomitant administration with other antipsychotics. While immediate discontinuation of the previous antipsychotic treatment may be acceptable for some patients, more gradual discontinuation may be most appropriate for others. In all cases, the period of overlapping antipsychotic administration should be minimized.
4.5 Missed Dose
If a dose is missed, then it should be taken as soon as possible unless it is close to the next dose. Two doses should not be taken at once.
5 OVERDOSAGE
There is limited clinical trial experience regarding human overdosage with REXULTI. ECG monitoring is recommended in the event of overdose.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Tablet, 0.25 mg, 0.5 mg, 1 mg, 2 mg, 3 mg, and 4 mg | corn starch, ferric oxide red (0.25 mg, 0.5 mg, 3 mg), ferric oxide yellow (0.25 mg, 0.5 mg, 1 mg, 2 mg), ferrosoferric oxide (0.25 mg, 2 mg, 3 mg), hydroxypropyl cellulose, hypromellose, lactose monohydrate, low-substituted hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, talc, and titanium dioxide |
REXULTI is available in bottles of 30 tablets and blister packs of 30 tablets.
REXULTI is available in the following tablet strengths:
Table 4: REXULTI Tablet Presentations
| Tablet Strength | Tablet Colour/Shape | Tablet Markings (Debossed with “BRX” and tablet strength on one side) |
|---|---|---|
| 0.25 mg | Light brown, film-coated Round; shallow convex; bevel-edged | “BRX” and “0.25” |
| 0.5 mg | Light orange, film-coated Round; shallow convex; bevel-edged | “BRX” and “0.5” |
| 1 mg | Light yellow, film-coated Round; shallow convex; bevel-edged | “BRX” and “1” |
| 2 mg | Light green, film-coated Round; shallow convex; bevel-edged | “BRX” and “2” |
| 3 mg | Light purple, film-coated Round; shallow convex; bevel-edged | “BRX” and “3” |
| 4 mg | White, film-coated Round; shallow convex; bevel-edged | “BRX” and “4” |
REXULTI contains the following inactive ingredients; corn starch, hydroxypropyl cellulose, hypromellose, lactose monohydrate, low-substituted hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, and talc (see 7 WARNINGS AND PRECAUTIONS, General, Lactose).
Colourants: ferric oxide red (0.25 mg, 0.5 mg, 3 mg), ferric oxide yellow (0.25 mg, 0.5 mg, 1 mg, 2 mg), ferrosoferric oxide (0.25 mg, 2 mg, 3 mg), and titanium dioxide.
7 WARNINGS AND PRECAUTIONS
Please see the 3 SERIOUS WARNINGS AND PRECAUTIONS BOX at the beginning of
PART I: HEALTH PROFESSIONAL INFORMATION.
General
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing REXULTI for patients who will be experiencing conditions which may contribute to an elevation in core body temperature (e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration).
Falls
Somnolence, postural hypotension, motor and sensory instability have been reported with the use of antipsychotics, including REXULTI, which may lead to falls and, consequently, fractures or other fall-related injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, assess the risk of falls when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Lactose
REXULTI tablets contain lactose. This should be considered when prescribing to patients with rare hereditary problems of galactose intolerance, lactase deficiency or glucose-galactose malabsorption (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
Cardiovascular
Orthostatic Hypotension
In the short-term, placebo-controlled clinical studies of REXULTI in subjects with schizophrenia, the incidence of orthostatic hypotension-related adverse reactions in REXULTI-treated patients compared to placebo subjects included: dizziness (2.3% versus 1.4%), orthostatic hypotension (0.4% versus 0.2%), and syncope (0.1% versus 0%). In the short-term, placebo-controlled clinical studies of REXULTI plus ADT in subjects with MDD, the incidence of orthostatic hypotension-related adverse reactions in REXULTI-treated subjects compared to placebo plus ADT subjects included: dizziness (2.6% versus 1.6%), dizziness postural (0.1% versus 0.4%), orthostatic hypotension (0.1% versus 0%), and syncope (0.1% versus 0.4%). In 12-week, placebo-controlled clinical studies of REXULTI in patients with AAD, the incidence of orthostatic hypotension-related adverse reactions in patients treated with REXULTI compared to patients treated with placebo included: dizziness (3.2% versus 3.4%), orthostatic hypotension (0.5% versus 0.5%), and syncope (0.2% versus 0.8%).
Adverse reactions associated with orthostatic hypotension can include dizziness, lightheadedness, and tachycardia. Generally, these risks are greatest at the beginning of treatment and during dose escalation. Patients at increased risk of these adverse reactions or at increased risk of developing complications from hypotension include those with dehydration, hypovolemia, treatment with antihypertensive medication, history of cardiovascular disease (e.g., heart failure, myocardial infarction, ischemia, or conduction abnormalities), history of cerebrovascular disease, as well as patients who are antipsychotic-naïve. In such patients, consider using a lower starting dosage and slower titration, and monitor orthostatic vital signs.
Patients with a recent history of myocardial infarction or unstable cardiovascular disease were excluded from clinical trials.
QT Interval
The effects of REXULTI on the QT/QTc interval were evaluated in a dedicated ECG study (see 10.2 Pharmacodynamics, Cardiac Electrophysiology). The trial involved administration of REXULTI at a therapeutic dose of 4 mg/day or a supratherapeutic dose of 12 mg/day for 11 days in 147 clinically stable patients with schizophrenia. On day 11, the maximum placebo-adjusted mean change from baseline in the QTcI interval was 8.3 ms (90% CI 3.7, 12.9) at 6 h post-dosing in the brexpiprazole 4 mg/day group (N=62) and 3.1 ms (90% CI -1.7, 8.0) at 4 h post-dosing in the brexpiprazole 12 mg/day group (N=53).
QTc prolongation may lead to an increased risk of ventricular arrhythmias including torsade de pointes. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Particular care should be exercised when administering REXULTI to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug (see 9 DRUG INTERACTIONS).
Risk factors for torsade de pointes in the general population include, but are not limited to, the following: female sex; age ≥65 years; baseline prolongation of the QT/QTc interval; presence of genetic variants affecting cardiac ion channels or regulatory proteins, especially congenital long QT syndromes; family history of sudden cardiac death at <50 years of age; cardiac disease (e.g., myocardial ischemia or infarction, congestive heart failure, cardiomyopathy, conduction system disease); history of arrhythmias; electrolyte disturbances (e.g., hypokalemia, hypomagnesemia, hypocalcemia) or conditions leading to electrolyte disturbances (e.g., persistent vomiting, eating disorders); bradycardia; acute neurological events (e.g., intracranial or subarachnoid haemorrhage, stroke, intracranial trauma); diabetes mellitus; and autonomic neuropathy.
When drugs that prolong the QTc interval are prescribed, healthcare professionals should counsel their patients concerning the nature and implications of the ECG changes, underlying diseases and disorders that are considered to represent risk factors, demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug. Patients should be advised to contact their healthcare provider immediately to report any new chest pain or discomfort, changes in heartbeat, palpitations, dizziness, lightheadedness, fainting, or changes in or new use of other medications.
Dependence/Tolerance
Brexpiprazole has not been systematically studied in humans for its potential for abuse, tolerance, or physical dependence. In drug dependence studies in animals, no withdrawal symptoms were observed upon abrupt cessation of dosing in rats and monkeys, and no frequent self-administration of brexpiprazole was observed in monkeys. While the clinical trials did not reveal any tendency for any drug-seeking behaviour, these observations were not systematic and it is not possible to predict on the basis of this limited experience the extent to which a CNS-active drug will be misused, diverted, or abused once marketed. Consequently, patients should be evaluated carefully for a history of drug abuse, and such patients should be observed closely for signs of REXULTI misuse or abuse (e.g., development of tolerance, increases in dose, drug-seeking behaviour).
Driving and Operating Machinery
Like other antipsychotic drugs, REXULTI has the potential to impair judgment, thinking, or motor skills. Because REXULTI may cause somnolence and impair motor skills, patients should be cautioned about performing activities requiring mental alertness, such as operating hazardous machinery, including motor vehicles, until they are reasonably certain that REXULTI therapy does not affect them adversely.
Endocrine and Metabolism
Hyperglycemia and Diabetes Mellitus
In both short-term placebo-controlled trials and long-term open-label trials with REXULTI, there have been reports of hyperglycemia in subjects treated with REXULTI. Diabetic ketoacidosis has occurred in patients with no reported history of hyperglycemia. Therefore, patients should have baseline and periodic monitoring of blood glucose and body weight.
Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies which did not include REXULTI, suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with atypical antipsychotics. Because REXULTI was not marketed at the time these studies were performed, it is not known if brexpiprazole is associated with this increased risk. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available.
Patients should have baseline and periodic monitoring of blood glucose and body weight. Any patient treated with atypical antipsychotics should also be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Weight Gain
Antipsychotic drugs have been associated with metabolic changes, including weight gain. Clinical monitoring of weight is recommended (see 8.2 Clinical Trial Adverse Reactions, Weight Gain).
Dyslipidemia
Undesirable alterations in lipids have been observed in subjects treated with atypical antipsychotics. Therefore, patients should have baseline and periodic monitoring of fasting lipid profile (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data, Fasting Lipids).
Hyperprolactinemia
Like other antipsychotics, REXULTI can elevate prolactin levels. Elevations associated with REXULTI treatment are generally mild and may decline during administration, however, in some infrequent cases the effect may persist during chronic administration (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Prolactin).
Hyperprolactinemia may suppress hypothalamic GnRH, resulting in reduced pituitary gonadotrophin secretion. This, in turn, may inhibit reproductive function by impairing gonadal steroidogenesis in both female and male patients. Galactorrhea, amenorrhea, gynecomastia, and impotence have been reported with prolactin-elevating compounds. Long-standing hyperprolactinemia when associated with hypogonadism may lead to decreased bone mineral density in both female and male patients.
Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of these drugs is considered in a patient with previously detected breast cancer. As is common with compounds which increase prolactin release, an increase in mammary gland neoplasia was observed in a REXULTI carcinogenicity study conducted in mice (see 16 NON-CLINICAL TOXICOLOGY). The physiological differences between rats and humans with regard to prolactin make the clinical significance of these findings unclear. To date, neither clinical nor epidemiological studies have shown an association between chronic administration of these drugs and mammary tumorigenesis.
Genitourinary
Although no cases of priapism were reported in clinical trials with REXULTI, rare cases of priapism have been reported with antipsychotic use. With other psychotropic drugs, this adverse reaction did not appear to be dose-dependent and did not correlate with the duration of treatment.
Hematologic
Blood Disorders
In clinical trial and/or post-marketing experience, events of leukopenia/neutropenia have been reported temporally related to antipsychotic agents. Agranulocytosis has also been reported. Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting REXULTI and then periodically throughout treatment.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug-induced leukopenia/neutropenia. Patients with a history of a clinically significant low WBC or drug-induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and discontinuation of REXULTI should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors.
Patients with clinically significant neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Discontinue REXULTI in patients with severe neutropenia (absolute neutrophil count <1x10⁹/L) and follow their WBC counts until recovery.
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs including REXULTI, in case reports and/or observational studies. When prescribing REXULTI all potential risk factors for VTE should be identified and preventative measures undertaken.
Immune
Hypersensitivity
Spontaneous post-market reports of serious hypersensitivity reactions, such as anaphylaxis, angioedema and facial swelling, rash and urticaria, have been reported with REXULTI (see 2 CONTRAINDICATIONS, 8.5 Post-Market Adverse Reactions).
Monitoring and Laboratory Tests
Should be monitored at baseline and periodically throughout treatment:
- Blood glucose, fasting lipid profile and body weight
- Complete blood count (CBC)
- White blood cell (WBC) and differential counts
- Prolactin
- Blood Pressure
Neurologic
Neuroleptic Malignant Syndrome (NMS)
Neuroleptic malignant syndrome is a potentially fatal symptom complex that has been reported in association with antipsychotic drugs, including brexpiprazole.
Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status (including catatonic signs), and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase (CPK), myoglobinuria (rhabdomyolysis), and acute renal failure.
In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.), and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
If NMS is suspected, immediately discontinue REXULTI and provide intensive symptomatic treatment and monitoring.
The management of NMS should include 1) immediate discontinuation of all antipsychotic drugs including REXULTI and other drugs not essential to therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment for uncomplicated NMS.
Patients with Parkinson’s Disease or Dementia with Lewy Bodies (DLB) may be at increased risk of NMS as well as having an increased sensitivity to antipsychotic medications. Manifestation of this increased sensitivity can include confusion, obtundation, and postural instability with frequent falls, in addition to extrapyramidal symptoms. Physicians should weigh the risks versus the benefits when prescribing antipsychotics, including REXULTI, to these groups of patients.
If a patient requires antipsychotic drug treatment after recovery from NMS, the potential reintroduction of therapy should be very carefully considered. The patient should be carefully monitored, since recurrence of NMS has been reported.
Tardive Dyskinesia
A syndrome of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome is highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome. Whether antipsychotic drugs differ in their potential to cause tardive dyskinesia is unknown.
The risk of developing tardive dyskinesia and the likelihood that it will become irreversible increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increases. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and, thereby, may possibly mask the underlying process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown.
Given these considerations, REXULTI should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that (1) is known to respond to antipsychotic drugs and (2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In such patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of tardive dyskinesia appear in a patient on REXULTI, drug discontinuation should be considered. However, some patients may require treatment with REXULTI despite the presence of the syndrome.
Seizure/Convulsion
As with other antipsychotic drugs, REXULTI should be used cautiously in patients with a history of seizures or with conditions that lower the seizure threshold. Post-marketing cases of seizures have been reported with REXULTI. Conditions that lower the seizure threshold may be more prevalent in a population of 65 years or older (see 8.5 Post-Market Adverse Reactions).
Psychiatric
Suicide
Completed suicide, attempted suicide, suicidal behaviour and suicidal ideation have been reported during post-market use of REXULTI. The possibility of a suicide attempt is inherent in psychotic illnesses and major depressive disorder (MDD). In addition, depression may be co-morbid with schizophrenia. The risk of suicide-related events during a depressive episode may persist until remission occurs. It is general clinical experience that the risk of suicide may increase in the early stages of recovery. Close supervision and appropriate clinical management of high-risk patients should accompany drug therapy. Prescriptions for REXULTI should be written for the smallest quantity of tablets consistent with good patient management, in order to reduce the risk of overdose (see 8.5 Post-Market Adverse Reactions).
Impulse-Control Disorders/Compulsive Behaviours
Post-marketing reports of impulse-control disorders including pathological gambling and compulsive shopping, binge eating, and hypersexuality and other compulsive behaviours have been reported very rarely in patients treated with brexpiprazole. Patients with a prior history of impulse-control disorder may be at increased risk and should be monitored carefully. Because patients may not recognize these behaviours as abnormal, it is important for prescribers to ask patients or their caregivers specifically about the development of new or increased impulse-control disorders or other compulsive behaviours while being treated with brexpiprazole. It should be noted that impulse-control symptoms can be associated with the underlying disorder. Compulsive behaviours may result in harm to the patient and others if not recognized. Consider dose reduction or stopping the medication if a patient develops such urges while taking brexpiprazole.
Skin
Severe Cutaneous Adverse Reactions
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP) are potentially life-threatening adverse drug reactions that have been reported with atypical antipsychotic exposure. SCARs commonly present as a combination of the following symptoms: malaise, mucosal ulceration, extensive cutaneous rash or exfoliative dermatitis, fever, lymphadenopathy and possible eosinophilia. Discontinue REXULTI if severe cutaneous adverse reactions occur.
7.1 Special Populations
7.1.1 Pregnant Women
Teratogenic effects
There are no adequate and well-controlled studies of REXULTI in pregnant women. It is not known whether REXULTI can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity.
In animal studies, brexpiprazole was not teratogenic and did not cause adverse developmental effects when administered during pregnancy at doses up to 24-fold in rats and 49-fold in rabbits, of the maximum recommended human dose (MRHD) of 4 mg/day on a mg/m2 body surface area for a 60 kg patient (see 16 NON-CLINICAL TOXICOLOGY). In a pregnant and lactating rat study, there was an increase in stillbirths and deaths of offspring at doses ≥ 10 mg/kg/day (24-fold MRHD on a mg/m2 basis).
Non-teratogenic effects
Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
REXULTI should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus.
Labour and Delivery: The effect of REXULTI on labour and delivery in humans is unknown. Parturition in rats was not affected by brexpiprazole.
7.1.2 Breast-feeding
REXULTI was excreted in milk of rats during lactation. It is not known whether REXULTI or its metabolites are excreted in human milk. Because of the potential for serious adverse reactions in nursing infants, it is recommended that women receiving REXULTI should not breast-feed.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness of REXULTI in patients under the age of 18 years have not been established and its use is not recommended. Weight gain has been observed with atypical antipsychotic use in pediatric and adolescent patient populations. Independent of any drug-specific effects, weight gain can be associated with adverse changes in other metabolic parameters (e.g., glucose and lipid metabolism). Abnormal childhood weight and metabolic status can have adverse effects on cardiovascular outcomes in adulthood. Weight gain and adverse effects on other metabolic parameters associated with atypical antipsychotics can be more frequent or severe in pediatric and adolescent patients than in adult patients. The long-term safety, including cardiometabolic effects and effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
7.1.4 Geriatrics
Schizophrenia and Major Depressive Disorder (MDD)
There were 248 (3%) patients 65 years of age and older in the overall clinical trials for schizophrenia and adjunctive therapy to antidepressants for MDD.
Clinical studies for the treatment of schizophrenia and MDD in patients treated with REXULTI did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger adult patients. In general, dose selection for the treatment of schizophrenia or MDD in an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 10 CLINICAL PHARMACOLOGY).
Agitation Associated with Alzheimer’s Dementia (AAD)
The total number of patients 65 years of age and older in the clinical trials for AAD was 641 (85%). Of the total number of patients treated in the studies for AAD, 257 (34%) were 65 to 74 years of age, while 384 (51%) were 75 years of age and older (see 14 CLINICAL TRIALS).
In clinical trials of geriatric patients (65 years of age and older) for the treatment of AAD, the incidence of overall adverse events (52.0% brexpiprazole versus 47.5% placebo), serious and severe adverse events (7.0% versus 4.5% and 5.9% versus 4.5%, respectively), study discontinuation due to adverse events (5.9% versus 3.6%), somnolence events (4.0% versus 1.8%), cardiovascular and cerebrovascular events (3.1% versus 2.1% and 0.4% versus 0.3%, respectively) was in general comparable between patients treated with brexpiprazole and placebo, with the exception of somnolence events. The incidence of falls (2.0%) and dizziness (3.2%) in patients treated with REXULTI was similar compared to patients treated with placebo (3.0% and 3.3%, respectively). No evidence of worsening or rapid cognitive decline based on a Mini-Mental State Examination (MMSE) score in comparison to placebo was observed. Over the entire clinical development of REXULTI in subjects with AAD, a higher mortality rate was observed in subjects exposed to brexpiprazole (N=10; 0.7%) compared to placebo (N=1; 0.2%).
Antipsychotic Drug Use in Elderly Patients with Dementia
Overall Mortality
Elderly patients with dementia treated with atypical antipsychotic drugs showed increased mortality compared to placebo in a meta-analysis of 13 placebo-controlled trials of various atypical antipsychotic drugs (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX). This imbalance in mortality rate was also observed in the trials evaluating the use of REXULTI in patients with AAD.
Cerebrovascular Adverse Events, Including Stroke in Elderly Patients with Dementia
In placebo-controlled trials with some atypical antipsychotics, there was a higher incidence of cerebrovascular adverse events (cerebrovascular accidents and transient ischemic attacks) including fatalities compared to placebo-treated subjects. There are insufficient data with REXULTI to know if there is an increased risk of cerebrovascular events associated with REXULTI (see also 3 SERIOUS WARNINGS AND PRECAUTIONS BOX). Geriatric subjects (65 years and older) with a history of stroke, transient ischemic attack, pulmonary embolism, or cerebral embolism were excluded from participation in clinical trials for the treatment of AAD.
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use, including REXULTI. Aspiration pneumonia is a common cause of morbidity and mortality in elderly patients, in particular those with advanced Alzheimer’s dementia. REXULTI and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Short-term and Long-term, Placebo-Controlled Trials of Adult Patients with Schizophrenia
The following findings are based on two 6-week, placebo-controlled, fixed-dose clinical trials, and one long-term 52-week double-blind placebo-controlled randomized-withdrawal trial for schizophrenia in which REXULTI was administered at daily doses between 1 mg and 4 mg. These are referred to as Trials 1, 2 and 3 respectively. In Trials 1 and 2, 852 patients received REXULTI at fixed daily doses of 1, 2 or 4 mg and 368 patients received placebo. In Trial 3, following an open-label stabilization period of up to 36 weeks, 97 patients received REXULTI at flexible daily doses between 1 and 4 mg and 104 patients received placebo in the double-blind randomized withdrawal period; the mean daily REXULTI dose was 3.6 mg at the last visit in the study. This trial was terminated after efficacy was demonstrated in an interim analysis, and only 23 patients (11%), 14 in the REXULTI group and 9 in the placebo group, completed the 52-weeks of the double-blind, controlled period.
Safety data is also available for 1265 patients who participated in uncontrolled, open-label studies and received REXULTI daily doses from 1 mg to 4 mg; 604 patients completed at least 26 weeks and 372 completed at least 52 weeks in the open-label studies.
Most Common Adverse Events: There are no common adverse events that meet the criteria incidence of ≥5% and at least twice the rate of placebo in the Trials 1 and 2, the 6-week, placebo-controlled, fixed-dose trials, or Trial 3, during the double-blind randomized-withdrawal period.
Adverse Events Reported as Reasons for Discontinuation of Treatment: A total of 7.8% (67/852) REXULTI-treated subjects and 14.7% (54/368) of placebo-treated subjects discontinued due to adverse events. There were no adverse events associated with discontinuation in subjects treated with REXULTI that were at least 2% and at least twice the placebo rate.
Treatment-emergent adverse events (TEAEs) associated with REXULTI (incidence of 2% or greater and REXULTI incidence greater than placebo) that occurred during acute therapy (up to 6-weeks in subjects with schizophrenia) are shown in Table 5.
Table 5: Treatment-emergent adverse events (TEAEs) with Incidence of 2% or More in Any Brex Group and Greater Than Placebo Group in Trials 1 and 2 (6-Week, Placebo-Controlled, Fixed-Dose Trials in Schizophrenia)
| System Organ Class MedDRA Preferred Term | Brexpiprazole (mg/day) | Placebo (N=368) % | |||
| 1 mg (N=120) % | 2 mg (N=368) % | 4 mg (N=364) % | ALL (N=852) % | ||
| Gastrointestinal disorders | |||||
| Diarrhoea | 1% | 3% | 3% | 3% | 2% |
| Dyspepsia | 6% | 2% | 3% | 3% | 2% |
| Dry mouth | 1% | 2% | 2% | 2% | 1% |
| Abdominal pain upper | 0% | 1% | 2% | 1% | 1% |
| Investigations | |||||
| Weight increased | 3% | 4% | 4% | 4% | 2% |
| Blood creatine phosphokinase increased | 4% | 2% | 2% | 2% | 1% |
| Musculoskeletal and connective tissue disorders | |||||
| Back pain | 1% | 2% | 3% | 2% | 2% |
| Pain in extremity | 3% | 2% | 2% | 2% | 1% |
| Myalgia | 2% | 1% | 1% | 1% | 1% |
| Nervous system disorders | |||||
| Akathisia | 4% | 5% | 7% | 6% | 5% |
| Tremor | 2% | 2% | 3% | 3% | 1% |
| Sedation | 2% | 2% | 3% | 2% | 1% |
| Dizziness | 2% | 1% | 3% | 2% | 1% |
| Psychiatric disorders | |||||
| Restlessness | 0% | 1% | 2% | 1% | 1% |
| Skin and Subcutaneous tissue disorders | |||||
| Rash | 3% | 2% | 1% | 2% | <1% |
In the longer-term randomized-withdrawal Trial 3, the general treatment-emergent adverse event profile for the initial 12 to 36-week single-blind REXULTI treatment phase of this study was comparable to the one characterized in the 6-week, placebo-controlled, fixed-dose trials 1 and 2 described above. In the double-blind, randomized withdrawal phase of the study, there was only one potentially drug-related adverse event that occurred at a rate greater than 2% and double that of placebo (tremor 3%). No additional safety concerns were noted, however, the exposure in the double-blind phase was limited (97 in REXULTI and 104 in placebo, about 40% overall completed at least 6 months, and 11% overall completed the 52 weeks).
Short-term Placebo-Controlled Clinical Trials in Adult Patients Receiving REXULTI as Adjunctive Treatment in Major Depressive Disorder (MDD)
The following findings are based on four phase 3, 6-week, placebo-controlled trials (331-10-228, 331-10-227, 331-13-214, 331-12-282), three of which were fixed-dose and one which was flexible-dose with an active reference. These are referred to as Trials 4, 5, 6 and 7 respectively.
In total, 1032 patients were treated with REXULTI in the 6-week trials. In Trials 4, 5 and 6, 835 patients received REXULTI at fixed daily doses of 1, 2 or 3 mg and 613 patients received placebo, added to their current antidepressant therapy (ADT). In Trial 7, 197 patients received REXULTI at flexible daily doses of 2 to 3 mg plus ADT, 100 patients received an active reference plus ADT, and 206 patients received placebo plus ADT. In Trial 7 the mean daily REXULTI dose was 2.2 mg at the last visit in the study.
Safety data are also available for 2240 patients who participated in uncontrolled, open-label studies and received REXULTI daily doses from 1 mg to 3 mg with ADT; 1304 patients completed at least 26 weeks and 1002 completed at least 52 weeks in the open-label studies.
Most Common Adverse Events: The most common adverse events (incidence of ≥ 5% in the REXULTI plus ADT group and at least twice the rate of placebo plus ADT) during short-term and long-term studies were akathisia and weight increased.
Adverse Events Reported as Reasons for Discontinuation of Treatment: In the 6-week studies a total of 2.4% (37/1520) REXULTI plus ADT-treated subjects and 0.7% (8/1132) of placebo plus ADT-treated subjects discontinued due to adverse events. There were no adverse event associated with discontinuation in subjects treated with REXULTI plus ADT that were at least 2% and at least twice the placebo plus ADT rate.
Treatment-emergent adverse events associated with the use of REXULTI plus ADT (incidence of 2% or greater and REXULTI plus ADT incidence greater than adjunctive placebo plus ADT) that occurred during acute therapy (6-weeks in patients with MDD) in fixed- and flexible-dose trials are shown in Table 6.
| Table 6: | TEAEs with Incidence of 2% or More in Any Brexpiprazole Dose Group (1 to 3 mg) and Greater than Placebo Group in Trials 4, 5, 6 and 7 (6-Week, Placebo-Controlled, Fixed-Dose and Flexible-Dose Trials in Adjunctive Treatment in MDD) | |||||
| System Organ Class MedDRA Preferred Term | Brexpiprazole (mg/day)+ADT | Placebo+ ADT (N=819) % | ||||
| 1 mg (N=226) % | 2 mg (N=380) % | 3 mg (N=229) % | 2-3 mg/day1 (N=197) % | ALL (N=1032) % | ||
| Subjects with any TEAE | 55% | 60% | 63% | 51% | 58% | 49% |
| Eye disorders | ||||||
| Vision blurred | 1% | 2% | 2% | 1% | 2% | 0% |
| Gastrointestinal Disorders | ||||||
| Constipation | 3% | 3% | 1% | 1% | 2% | 1% |
| Dry mouth | 1% | 3% | 1% | 1% | 2% | 1% |
| Flatulence | 2% | 1% | 1% | 1% | 1% | 1% |
| Diarrhea | 4% | 3% | 2% | 0% | 2% | 3% |
| General Disorders and Administration Site Conditions | ||||||
| Fatigue | 3% | 2% | 5% | 2% | 3% | 1% |
| Asthenia | 0% | <1% | 0% | 2% | 1% | <1% |
| Infections and Infestations | ||||||
| Nasopharyngitis | 7% | 3% | 3% | 5% | 4% | 3% |
| Investigations | ||||||
| Weight Increased | 7% | 7% | 6% | 4% | 6% | 2% |
| Blood cortisol decreased | 4% | 0% | 3% | 0% | 1% | 1% |
| Blood prolactin increased | <1% | 1% | 3% | 0% | 1% | 0% |
| Metabolism and Nutrition Disorders | ||||||
| Increased Appetite | 3% | 4% | 2% | 3% | 3% | 2% |
| Musculoskeletal and Connective Tissue disorders | ||||||
| Back Pain | 1% | 2% | 0% | 1% | 1% | 2% |
| Nervous System Disorders | ||||||
| Akathisia | 4% | 8% | 14% | 6% | 8% | 3% |
| Headache | 9% | 4% | 6% | 6% | 6% | 6% |
| Somnolence | 4% | 5% | 6% | 6% | 5% | 1% |
| Tremor | 4% | 2% | 5% | 1% | 3% | 1% |
| Dizziness | 1% | 4% | 2% | 4% | 3% | 1% |
| Psychiatric Disorders | ||||||
| Restlessness | 2% | 6% | 4% | 3% | 4% | 1% |
| Insomnia | 2% | 3% | 3% | 3% | 3% | 2% |
| Anxiety | 2% | 3% | 4% | 1% | 2% | 1% |
| Irritability | 1% | 1% | <1% | 2% | 1% | 1% |
Legend: ADT=antidepressant
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
Placebo-Controlled Trials of Adult Patients with Agitation Associated with Alzheimer’s Dementia (AAD)
The following findings are based on two phase 3, 12-week, placebo-controlled, fixed-dose trials (331-12-283, 331-14-213) and one phase 3, 12-week, placebo-controlled, flexible-dose trial (331-12-284). These are referred to as Trials 10, 11 and 12 respectively.
In total 655 patients were treated with REXULTI in the 12-week trials (0.5-3 mg). In Trial 10, 297 patients received REXULTI at fixed daily doses of 0.5, 1 or 2 mg and 135 patients received placebo (the 0.5 mg arm was not completed). In Trial 11, 226 patients received REXULTI at fixed daily doses of 2 or 3 mg, and 116 patients received placebo. In Trial 12, 132 patients received REXULTI at a flexible daily dose ranging from 0.5 to 2 mg, and 137 patients received placebo.
The safety of REXULTI was evaluated in 655 patients (51 to 90 years of age), with a probable diagnosis of AAD, who participated in three 12-week placebo-controlled, fixed-dose and flexible-dose clinical studies in which REXULTI was administered at daily doses of 0.5 mg to 3 mg (see 14 CLINICAL TRIALS). Eligible patients, who completed Trial 11, were also able to participate in an additional 12-week, active-treatment extension trial (331-201-00182, referred as Trial 13). There were no additional safety findings during the extension trial.
Most Common Adverse Events: None of the adverse events reported in Trials 10, 11 and 12 met the criteria of most common adverse events (incidence of ≥ 5% in the REXULTI (all brexpiprazole) group and at least twice the rate of placebo).
Adverse Events Reported as Reasons for Discontinuation of Treatment: In three 12-week placebo-controlled, fixed-dose and flexible-dose clinical studies, a total of 6.3% (41/655) of patients treated with REXULTI and 3.4% (13/388) of patients treated with placebo discontinued due to adverse reactions.
Adverse reactions associated with REXULTI (incidence of 2% or greater and REXULTI incidence greater than placebo) during the 12-week clinical trials in geriatric patients for treatment of AAD are shown in Table 7.
| Table 7: | TEAEs with Incidence of 2% or More in Any Brexpiprazole Dose Group (0.5 to 3 mg) and Greater than Placebo Group in Trials 10, 11 and 12 (12-Week, Placebo-Controlled, Fixed-Dose and Flexible-Dose Trials in AAD) | ||||||
| System Organ Class MedDRA Preferred Term | Brexpiprazole (mg/day) | Placebo (N=388) % | |||||
| ≤ 1 mg1 (N=157) % | 2 mg2 (N=213) % | 3 mg2 (N=153) % | 2 and 3 mg (N=366) % | 0.5–2 mg3 (N=132) % | ALL (N=655) % | ||
| Infections and Infestations | |||||||
| Nasopharyngitis | 3% | 2% | 3% | 3% | 3% | 3% | 3% |
| Urinary Tract Infection | 2% | 3% | 3% | 3% | 2% | 3% | 2% |
| Nervous System Disorders | |||||||
| Dizziness | <1% | 4% | 3% | 4% | 5% | 3% | 3% |
| Somnolence | 1% | 3% | 3% | 3% | 6% | 3% | 2% |
| Psychiatric Disorders | |||||||
| Insomnia | 5% | 4% | 2% | 3% | 4% | 4% | 3% |
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
In Trials 10, 11 and 12, the majority of TEAEs were mild or moderate in severity. The general treatment-emergent adverse event profile of the 12-week long-term active-treatment extension trial (Trial 13) was comparable to the one characterized in the 12-week, placebo-controlled, fixed-dose and flexible-dose trials (Trials 10, 11 and 12) and no additional safety concerns were noted.
Selected Adverse Events
Extrapyramidal Symptoms (EPS)
Schizophrenia
In Trials 1 and 2, the incidence of reported EPS-related events, excluding akathisia events, was 5.1% versus 3.5% for placebo-treated subjects. The incidence of akathisia events for REXULTI-treated subjects was 5.4% versus 4.9% for placebo-treated subjects. Akathisia was reported more often during Weeks 1 through 3 and was mild to moderate in severity. The incidence of EPS-related TEAEs is presented in Table 8.
| Table 8: Incidence of EPS-related TEAEs in Short-term Controlled Schizophrenia Trials 1 and 2 | ||||||||||||
EPS Class Adverse Event MedDRA Preferred Term | Brexpiprazole (mg/day) | Placebo N = 368 % | ||||||||||
| 1 mg N = 120 % | 2 mg N = 368 % | 4 mg N = 364 % | ALL N = 852 % | |||||||||
| Subjects with any adverse event | 7% | 10% | 14% | 11% | 8% | |||||||
| Total Akathisia Eventsa | 5% | 5% | 7% | 6% | 5% | |||||||
| Total Dyskinetic Eventsb | 0% | <1% | <1% | <1% | <1% | |||||||
| Total Dystonic Eventsc | 2% | 1% | 2% | 2% | 2% | |||||||
| Total Parkinsonian Eventsd | 2% | 4% | 6% | 4% | 2% | |||||||
| Total Residual Eventse | 0% | 0% | <1% | <1% | 0% | |||||||
a Total Akathisia events includes adverse event terms: akathisia, psychomotor hyperactivity
b Total Dyskinetic events includes adverse events: dyskinesia, tardive dyskinesia
c Total Dystonic events includes adverse event terms: dystonia, muscle rigidity, muscle spasms
d Total Parkinsonian events includes adverse event terms: bradykinesia, extrapyramidal disorder, parkinsonism, tremor e Total Residual events includes adverse event terms: muscle twitching
In Trials 1 and 2, data was objectively collected on the Simpson Angus Rating Score (SAS) for extrapyramidal symptoms (EPS), the Barnes Akathisia Global Score (BARS) for akathisia and the Abnormal Involuntary Movement Score (AIMS) for dyskinesia. The incidence of EPS change is presented in Table 9.
Table 9: Change in EPS Compared to Placebo in Schizophrenia Trials 1 and 2
| Proportion of Subjects with Shifts (worsening) from Baseline | ||||
|---|---|---|---|---|
| Brexpiprazole (mg/day) | ||||
| 1 mg | 2 mg | 4 mg | Placebo | |
| AIMSa Total Score | 1% (1/120)* | 3% (12/361)* | 4% (13/362)* | 4% (13/361)* |
| BARSb Global Score | 1% (1/119)* | 1% (2/361)* | 2% (9/362)* | 1% (5/362)* |
| SASc Total Score | 6% (7/119)* | 6% (21/356)* | 8% (28/357)* | 5% (19/356)* |
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
a Abnormal Involuntary Movement Scale - %shifts from ≤1 at baseline to any post-baseline value ≥2
b Barnes Akathisia Rating Scale- %shifts from ≤2 at baseline to any post-baseline value >2
c Simpson Angus Scale- %shifts from ≤3 at baseline to any post-baseline value >3
Table 10 presents the reported incidence of concomitant medications used to treat EPS-related TEAEs, including akathisia.
| Table 10: Incidence of Reported Concomitant Use to Treat EPS-related TEAEs for Short-term Controlled Schizophrenia Trials 1 and 2 | |||||||
Drug Class Medication Preferred Name | Brexpiprazole (mg/day) | Placebo N = 368 n (%) | |||||
| 1 mg N = 120 n (%) | 2 mg N = 368 n (%) | 4 mg N = 364 n (%) | |||||
| Total using 1 or more medications | 5 (4.2) | 23 (6.3) | 34 (9.3) | 19 (5.2) | |||
| Anti-Parkinson Drugs | 4 (3.3) | 18 (4.9) | 26 (7.1) | 15 (4.1) | |||
| Beta Blocking Agents | 1 (0.8) | 8 (2.2) | 11 (3.0) | 6 (1.6) | |||
Adjunctive Treatment in Major Depressive Disorder (MDD)
In Trials 4, 5 and 6, the incidence of reported EPS-related events, excluding akathisia events, was 5.3% versus 2.4% for placebo-treated subjects. The incidence of akathisia events for REXULTI-treated subjects was dose-dependent. In most cases, akathisia was assessed as mild or moderate in severity. Discontinuations due to akathisia were reported only for REXULTI-treated subjects (0.3% for REXULTI 2 mg/day plus ADT, 2.2% for REXULTI 3 mg/day plus ADT).
In Trial 7, the incidence of reported EPS-related events, excluding akathisia events, was 2.5% versus 0.5% for placebo-treated subjects. The incidence of akathisia events for REXULTI-treated subjects was 6.1% (2-3 mg) in the REXULTI plus ADT group versus 1.9% in the placebo plus ADT group. In most cases, akathisia was assessed as mild or moderate in severity.
The incidence of EPS-related TEAEs in the short-term fixed-dose and flexible-dose trials is presented in Table 11.
| Table 11: | Incidence of EPS-related TEAEs in Short-term Fixed-dose Trials 4, 5, and 6 and Short-term Flexible-dose Trial 7 in Adjunctive Treatment in MDD | |||||||||||||
| EPS Category | Brexpiprazole (mg/day)+ADT | Placebo+ ADT N = 819 % | ||||||||||||
| 1 mg N = 226 % | 2 mg N = 380 % | 3 mg N = 229 % | 2-3 mg1 N = 197 % | ALL N = 1032 % | ||||||||||
| Subjects with any adverse event | 10% | 13% | 18% | 9% | 13% | 5% | ||||||||
| Total Akathisia Eventsa | 4% | 8% | 14% | 6% | 8% | 3% | ||||||||
| Total Dyskinesia Eventsb | <1% | 0% | 0% | 0% | <1% | 0% | ||||||||
| Total Dystonic Eventsc | 1% | 1% | 2% | 2% | 1% | 1% | ||||||||
| Total Parkinsonian Eventsd | 5% | 4% | 6% | 1% | 4% | 2% | ||||||||
| Total Residual Eventse | <1% | 1% | 0% | 0% | 1% | 0% | ||||||||
Legend: ADT=antidepressant
a Total Akathisia events includes adverse event terms: akathisia
bTotal Dyskinetic events includes adverse events: dyskinesia
c Total Dystonic events includes adverse event terms: dystonia, muscle contractions involuntary, muscle rigidity, muscle spasms d Total Parkinsonian events includes adverse event terms: cogwheel rigidity, extrapyramidal disorder, hypertonia, hypokinesia, parkinsonian gait, parkinsonian rest tremor, parkinsonism, tremor
e Total Residual events includes adverse event terms: muscle twitching
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
In Trials 4, 5, 6 and 7, data was objectively collected on the Simpson Angus Rating Score (SAS) for extrapyramidal symptoms (EPS), the Barnes Akathisia Global Score (BARS) for akathisia and the Abnormal Involuntary Movement Score (AIMS) for dyskinesia. The incidence of EPS change is presented in Table 12.
Table 12: Change in EPS Compared to Placebo in MDD Trials 4, 5, 6 and 7
| Proportion of Subjects with Shifts (worsening) from Baseline | |||||
|---|---|---|---|---|---|
| Brexpiprazole (mg/day)+ADT | |||||
| 1 mg | 2 mg | 3 mg | 2-3 mg1 | Placebo+ADT | |
| AIMSa Total Score | 3% (6/222)* | 3% (11/367)* | 3% (6/220)* | 0% (0/191)* | 1% (6/806)* |
| BARSb Global Score | 1% (3/220)* | 6% (23/373)* | 6% (12/220)* | 4% (7/191)* | 2% (14/810)* |
| SASc Total Score | 1% (3/221)* | 4% (16/372)* | 5% (10/220)* | 0% (0/191)* | 2% (16/811)* |
Legend: ADT=antidepressant
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
a Abnormal Involuntary Movement Scale - %shifts from ≤1 at baseline to any post-baseline value ≥2
b Barnes Akathisia Rating Scale- %shifts from ≤2 at baseline to any post-baseline value >2
c Simpson Angus Scale- %shifts from ≤3 at baseline to any post-baseline value >3
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
Table 13 presents the reported incidence of concomitant medications used to treat EPS-related TEAEs, including akathisia during Trials 4, 5, 6 and 7.
| Table 13: | Incidence of Reported Concomitant Use to Treat EPS-related TEAEs for Short-term Controlled MDD Adjunctive Trials 4, 5, 6 and 7 | ||||||||
| Drug Class Medication Preferred Name | Brexpiprazole (mg/day)+ADT | Placebo+ ADT N = 819 n (%) | |||||||
| 1 mg N = 226 n (%) | 2 mg N = 380 n (%) | 3 mg N = 229 n (%) | 2-3 mg1 N = 197 n (%) | ||||||
Total using 1 or more medications | 2 (0.9) | 15 (3.9) | 16 (7.0) | 7 (3.6) | 7 (0.9) | ||||
| Anti-Parkinson Drugs | 2 (0.9) | 2 (0.5) | 9 (3.9) | 1 (0.5) | 2 (0.2) | ||||
| Beta Blocking Agents | 0 (0.0) | 12 (3.2) | 7 (3.1) | 6 (3.0) | 5 (0.6) | ||||
| Psycholeptics | 0 (0.0) | 3 (0.8) | 5 (2.2) | 0 (0) | 0 (0.0) | ||||
Legend: ADT=antidepressant
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
Agitation Associated with Alzheimer’s Dementia (AAD)
In Trials 10, 11 and 12, the incidence of reported EPS-related adverse reactions, excluding akathisia events, was 5% for REXULTI-treated patients versus 3% for placebo-treated patients. The incidence of akathisia events for REXULTI-treated patients was 1% versus 0% for placebo-treated patients.
The incidence of EPS-related TEAEs in the short-term fixed-dose and flexible-dose trials is presented in Table 14.
| Table 14: | Incidence of EPS-related TEAEs in the 12-Week, Placebo-Controlled, Fixed-Dose and Flexible-Dose Trials in AAD | ||||||||||||||||
| EPS Category | Brexpiprazole (mg/day) | Placebo N = 388 % | |||||||||||||||
| ≤1 mg1 N = 157 % | 2 mg2 N = 213 % | 3 mg2 N = 153 % | 2 and 3 mg N = 366 % | 0.5-2 mg3 N = 132 % | ALL N = 655 % | ||||||||||||
| Subjects with any EPS-related adverse event | 3% | 5% | 4% | 5% | 10% | 5% | 3% | ||||||||||
| Total Akathisia Eventsa | <1% | 1% | 2% | 2% | 3% | 2% | <1% | ||||||||||
| Total Dyskinesia Eventsb | 0% | 0% | 0% | 0% | 2% | <1% | <1% | ||||||||||
| Total Dystonic Eventsc | <1% | <1% | 0% | <1% | 0% | <1% | <1% | ||||||||||
| Total Parkinsonian Eventsd | 2% | 3% | 2% | 3% | 6% | 3% | 3% | ||||||||||
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
a Total Akathisia events includes adverse event terms: akathisia, extrapyramidal disorder, psychomotor hyperactivity bTotal Dyskinetic events includes adverse events: dyskinesia
c Total Dystonic events includes adverse event terms: muscle spasms, musculoskeletal stiffness
d Total Parkinsonian events includes adverse event terms: bradykinesia, bradyphrenia, gait disturbance, hypertonia, hypokinesia, muscle rigidity, parkinsonism, tremor
In the 12-week placebo-controlled, fixed-dose and flexible-dose trials in AAD, data were collected with the Simpson-Angus Rating Scale (SAS) for EPS, the Barnes Akathisia Rating Scale (BARS) for akathisia and the Abnormal Involuntary Movement Scale (AIMS) for dyskinesia. The mean change from baseline at last visit for REXULTI-treated patients for the SAS, BARS and AIMS was comparable to placebo-treated patients. The percentages of patients who shifted from normal to abnormal were similar between REXULTI- and placebo-treated subjects for the BARS and AIMS but greater in REXULTI-treated patients versus placebo for the SAS (6% versus 2%). The incidence of EPS change is presented in Table 15.
Table 15: Change in EPS Compared to Placebo in AAD Trials 10, 11 and 12
| Proportion of Subjects with Shifts (worsening) from Baseline | |||||||
|---|---|---|---|---|---|---|---|
| Brexpiprazole (mg/day) | |||||||
| ≤1 mg1 | 2 mg2 | 3 mg2 | 2 and 3 mg | 0.5-2 mg3 | ALL | Placebo | |
| AIMSa Total Score | 2% (3/152)* | 1% (2/208)* | 3% (4/141)* | 2% (6/349)* | 3% (4/130)* | 2% (13/631)* | 1% (5/378)* |
| BARSb Global Score | <1% (1/156)* | 0% (0/210)* | 0% (0/142)* | 0% (0/352)* | <1% (1/132)* | <1% (2/640)* | <1% (1/379)* |
| SASc Total Score | 4% (6/156)* | 8% (16/209)* | 4% (6/141)* | 6% (22/350)* | 6% (8/132)* | 6% (36/638)* | 2% (8/378)* |
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
a Abnormal Involuntary Movement Scale - %shifts from ≤1 at baseline to any post-baseline value ≥2
b Barnes Akathisia Rating Scale- %shifts from ≤2 at baseline to any post-baseline value >2
c Simpson Angus Scale- %shifts from ≤3 at baseline to any post-baseline value >3
Weight Gain
Schizophrenia
Table 16 shows weight gain data at last visit and percentage of adult subjects with ≥7% increase in body weight at any visit from Trials 1 and 2.
Table 16: Changes in Weight (kg) - Trials 1 and 2 (up to 6 weeks)
| Brexpiprazole (mg/day) | |||||
| 1 mg/day N=120 | 2 mg/day N=362 | 4 mg/day N=362 | Placebo N=362 | ||
| Mean Change from Baseline (kg) at Last Visit | |||||
| All Subjects | +1.0 | +1.2 | +1.2 | +0.2 | |
| Proportion of Subjects with a ≥7% Increase in Body Weight (kg) at Any Visit | |||||
| N=120 | N=368 | N=364 | N=368 | ||
| ≥7% Increase | 10.0% (12/120) | 10.5% (38/362) | 10.2% (37/362) | 4.1% (15/362) | |
The percentage of subjects in the 6-week Trials 1 and 2 with an increase of ≥7% in body weight was 10.5% and 10.2% in the REXULTI 2 and 4 mg/day group respectively, compared with 4.1% in the placebo group.
During the longer-term randomized-withdrawal Trial 3 the proportion of subjects with a ≥7% increase in body weight at any visit was 5.2% (5/96) in the REXULTI-treated group compared to 1.0% (1/104) in the placebo group. The proportion of subjects with a ≥7% decrease in body weight at any visit was 9.3% (9/96) in the REXULTI-treated group compared to 15.3% (16/104) in the placebo group. In the stabilization phase of this trial, the proportion of subjects with a ≥7% increase in body weight at any visit was 11.3% (52/462) and with a ≥7% decrease in body weight at any visit was 3.9% (18/462).
In the long-term, open-label schizophrenia studies, the mean change in body weight from baseline to last visit was 1.0 kg (N=1468). The proportion of subjects with a ≥7% increase in body weight at any visit was 17.9% (226/1257) and with a ≥7% decrease in body weight at any visit was 8.2% (104/1257). Weight gain led to discontinuation of study medication in 0.4% (5/1265) of subjects.
Adjunctive Treatment in Major Depressive Disorder (MDD)
Table 17 shows weight gain data at last visit and percentage of adult subjects with ≥7% increase in body weight at any visit from Trials 4, 5, 6 and 7.
Table 17: Changes in Weight (kg) - Trials 4, 5, 6 and 7 (up to 6 weeks)
| Brexpiprazole (mg/day)+ADT | ||||||
1 mg/day N=225 | 2 mg/day N=379 | 3 mg/day N=228 | 2-3 mg/day1 N=193 | Placebo+ADT N=819 | ||
| Mean Change from Baseline (kg) at Last Visit | ||||||
| All Subjects | +1.3 | +1.6 | +1.6 | +1.1 | +0.3 | |
| Proportion of Subjects with a ≥7% Increase in Body Weight (kg) at Any Visit | ||||||
| N=225 | N=379 | N=229 | N=193 | N=609 | ||
| ≥7% Increase | 4.9% (11/225) | 4.5% (17/379) | 2.2% (5/228) | 5.7% (11/193) | 1.8% (15/814) | |
Legend: ADT=antidepressant
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
In the long-term open-label studies the proportion of subjects with a ≥7% increase in body weight at last visit (LOCF) was 22.1% (494/2232) and with a ≥7% decrease in body weight was 3.2% (72/2232). At 52 weeks (completers), the proportion of subject with a ≥7% increase in body weight at was 28.2 % (286/1013) and with a ≥7% decrease in body weight was 3.7% (37/1013). Weight gain led to discontinuation of study medication in 3.8% (84/2240) of subjects.
Agitation Associated with Alzheimer’s Dementia (AAD)
In the 12-week placebo-controlled, fixed-dose and flexible-dose clinical studies in patients (51 to 90 years of age) with AAD, the mean changes in body weight from baseline to the last visit were similar in patients treated with REXULTI and patients treated with placebo. The proportion of the patients with a ≥7% increase in body weight (kg) at any visit were 1.7% in REXULTI compared to 0.8% in placebo group.
Table 18 shows weight gain data at last visit and percentage of adult subjects with ≥7% increase in body weight at any visit from Trials 10, 11, and 12.
Table 18: Changes in Weight (kg) - Trials 10, 11, and 12 (up to 12 weeks)
| Brexpiprazole (mg/day) | ||||||||
≤1 mg/day1 N=157 | 2 mg/day2 N=213 | 3 mg/day2 N=153 | 2 and 3 mg/day N=366 | 0.5-2 mg/day3 N=132 | ALL N=655 | Placebo N=388 | ||
| Mean Change from Baseline (kg) at Last Visit | ||||||||
| All Subjects | -0.1 | +0.2 | +0.1 | +0.2 | +0.2 | +0.1 | -0.2 | |
| Proportion of Subjects with a ≥7% Increase in Body Weight (kg) at Any Visit | ||||||||
| N=157 | N=213 | N=153 | N=366 | N=132 | N=655 | N=388 | ||
| ≥7% Increase | 2% (3/157) | 1.9% (4/211) | 1.3% (2/149) | 2% (6/360) | 2% (2/132) | 2% (11/649) | <1% (3/382) | |
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
Patients (55 to 90 years of age) from the 12-week placebo-controlled, fixed-dose clinical study, who rolled over into a 12-week, active-treatment extension study did not show any overall change in weight (kg) from baseline to last visit in association with REXULTI. In the study, 3% of patients demonstrated a ≥7% increase in body weight, and 4% demonstrated a ≥7 % decrease in body weight from baseline to last visit.
Constipation
Patients should be advised of the risk of severe constipation during REXULTI treatment, and they should tell their doctor if constipation occurs or worsens, since they may need medical intervention.
8.3 Less Common Clinical Trial Adverse Reactions
Other adverse reactions (<2% frequency in REXULTI-treated patients and greater than placebo) reported in the short-term, placebo-controlled trials in subjects with schizophrenia, MDD and AAD (N=3581) and in the long-term placebo-controlled trials in subjects with schizophrenia (N=97), are shown below. The following listing does not include adverse reactions: 1) already listed in previous tables or elsewhere in the labeling, 2) for which a drug cause was remote, 3) which were so general as to be uninformative, 4) which were not considered to have clinically significant implications, or 5) which occurred at a rate equal to or less than placebo.
Blood and Lymphatic System Disorders:
Infrequent: Anemia
Cardiovascular Disorders:
Infrequent: Vision Blurred, Sinus Bradycardia, Atrioventricular Block First Degree, Palpitations
Endocrine Disorders:
Infrequent: Hyperprolactinemia
Eye Disorders:
Infrequent: Lacrimation increased, Blepharospasm
Gastrointestinal Disorders:
Infrequent: Salivary Hypersecretion, Dental Caries, Abdominal Distension, Gastroesophageal Reflux Disease, Toothache
General Disorders & Administration Site Conditions:
Infrequent: Asthenia, Pyrexia, Chest Pain
Infections and Infestations:
Frequent: Upper Respiratory Tract Infection
Infrequent: Bronchitis, Conjunctivitis, Urinary Tract Infection
Investigations:
Infrequent: Hepatic Enzyme Increased, Blood Triglycerides Increased, Aspartate Aminotransferase Increased
Musculoskeletal and Connective Tissue Disorders:
Infrequent: Musculoskeletal Pain, Musculoskeletal Stiffness, Rhabdomyolysis
Nervous System Disorders:
Infrequent: Psychomotor Activity, Extrapyramidal Disorder
Psychiatric Disorders:
Infrequent: Abnormal Dreams, Bruxism, Tension
Respiratory, Thoracic and Mediastinal Disorders:
Infrequent: Cough, Dyspnea
Skin and Subcutaneous Tissue Disorders:
Infrequent: Night Sweats
Vascular Disorders:
Infrequent: Hypertension, Orthostatic Hypotension, Hypotension, Flushing
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Fasting Glucose
Schizophrenia
In the 6-week Trials 1 and 2, the proportion of patients with changes in fasting glucose to post-baseline high (≥126 mg/dL) results were comparable between REXULTI and placebo treated subjects.
In the longer-term randomized-withdrawal Trial 3, 7% of patients with normal baseline fasting glucose (N=388) had changes to high fasting glucose during the single-blind REXULTI treatment in the Stabilization phase. During the double-blind phase, from the patients with normal baseline fasting glucose, 4.5% in the REXULTI group (3/66) and 0% in the placebo group (0/62) had changes to high fasting glucose.
In the long-term, open-label schizophrenia studies, 7% of patients with normal baseline fasting glucose experienced a shift from normal to high while taking REXULTI, 17% of subjects with borderline fasting glucose experienced shifts from borderline to high. Combined, 9% of subjects with normal or borderline fasting glucose experienced shifts to high fasting glucose during the long-term schizophrenia studies.
Adjunctive Treatment in Major Depressive Disorder (MDD)
In the 6-week Trials 4, 5 and 6, the proportion of patients with changes in fasting glucose from normal values at baseline (i.e., < 100 mg/dL) to post-baseline high (≥126 mg/dL) results were comparable between REXULTI plus ADT and placebo plus ADT treated subjects. In Trial 7, the percentage of patients with a shift in fasting glucose from a normal value (i.e., < 100 mg/dL) at baseline to a high value (i.e., ≥ 126 mg/dL) was 0.8% in the flexible-dose REXULTI plus ADT group compared to 0% in the placebo plus ADT group. Mean changes from baseline to last visit in the REXULTI plus ADT groups were similar to the placebo plus ADT group for HbA1c.
In the long-term, open-label MDD studies, 5.2% of patients with normal baseline fasting glucose experienced a shift from normal to high while taking REXULTI plus ADT, 24.4% of subjects with borderline fasting glucose experienced shifts from borderline to high. Combined, 9.1% of subjects with normal or borderline fasting glucose experienced shifts to high fasting glucose during the long-term MDD studies.
Agitation Associated with Alzheimer’s Dementia (AAD)
In the 12-week placebo-controlled, fixed-dose and flexible-dose studies in patients (51 to 90 years of age) with AAD, the proportions of patients with shifts in fasting glucose from normal (<100 mg/dL) to high (≥126 mg/dL) were similar in patients treated with REXULTI (14%) and patients treated with placebo (14%).
Of the patients (55 to 90 years of age) from the 12-week placebo-controlled, fixed-dose clinical study, who rolled over into a 12-week, active-treatment extension study, 14% of patients with normal baseline fasting glucose experienced a shift from normal (<100 mg/dL) to high (≥126 mg/dL) while taking REXULTI; 24% of patients with impaired fasting glucose experienced shifts from impaired (≥100 and <126 mg/dL) to high. Combined, 18% of patients with normal or impaired fasting glucose experienced shifts to high fasting glucose.
Fasting Lipids
Schizophrenia
In Trials 1 and 2, the proportion of patients with clinically significant changes from baseline in fasting total cholesterol, LDL cholesterol, and HDL cholesterol were similar in REXULTI- and placebo-treated subjects. Table 19 shows the proportions of subjects with changes in fasting triglycerides.
Table 19: Change in Fasting Triglycerides in Trials 1 and 2 (up to 6 weeks)
| Proportion of Subjects with Shifts Baseline to Post-Baseline | |||||
| Brexpiprazole (mg/day) | |||||
| 1 mg/day | 2 mg/day | 4 mg/day | Placebo | ||
| Triglycerides Normal to High (<150 mg/dL to ≥200 and <500 mg/dL) | 10% (7/72)* | 8% (19/232)* | 10% (22/226)* | 6% (15/253)* | |
| Normal/Borderline to Very High (<200 mg/dL to ≥500 mg/dL) | 0% (0/94)* | 0% (0/283)* | 0.4% (1/283)* | 0% (0/303)* | |
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
In the longer-term randomized-withdrawal Trial 3, 22% of patients with normal baseline fasting triglycerides (N=394) had changes to high or very high fasting triglycerides during single-blind REXULTI treatment in the Stabilization phase. During the double-blind phase, from the patients with normal baseline fasting triglycerides, 7% in the REXULTI group (4/57) and 0% in the placebo group (0/60) had changes to high fasting triglycerides.
In the long-term open-label studies, shifts in baseline fasting cholesterol from normal to high were reported in 6% (total cholesterol), 3% (LDL cholesterol), and shifts in baseline from normal to low were reported in 20% (HDL cholesterol) of patients taking REXULTI. Of patients with normal baseline triglycerides, 14% experienced shifts to high, and 0.3% experienced shifts to very high triglycerides. Combined, 0.5% of subjects with normal or borderline fasting triglycerides experienced shifts to very high fasting triglycerides during the long-term schizophrenia studies.
Adjunctive Treatment in Major Depressive Disorder (MDD)
In Trials 4, 5, 6, and 7, the proportion of patients with clinically significant changes from baseline in fasting total cholesterol, LDL cholesterol, and HDL cholesterol were similar in REXULTI plus ADT- and placebo plus ADT-treated subjects. Table 20 shows the proportions of subjects with changes in fasting triglycerides in Trials 4, 5, 6 and 7.
Table 20: Change in Fasting Triglycerides in Trials 4, 5, 6 and 7 (up to 6 weeks)
| Proportion of Subjects with Shifts Baseline to Post-Baseline | ||||||
| Brexpiprazole (mg/day)+ADT | ||||||
| 1 mg/day | 2 mg/day | 3 mg/day | 2-3 mg/day1 | Placebo+ADT | ||
Triglycerides Normal to High (<150 mg/dL to ≥200 and <500 mg/dL) | 5% (7/145)* | 8% (19/226)* | 9% (13/150)* | 9% (11/120)* | 5% (25/522)* | |
| Normal/Borderline to Very High (<200 mg/dL to ≥500 mg/dL) | 0% (0/177)* | 0.4% (1/275)* | 0% (0/179)* | 0% (0/152)* | 0% (0/618)* | |
Legend: ADT=antidepressant
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
In the long-term open-label studies, shifts in baseline fasting cholesterol from normal to high were reported in 8.7% (total cholesterol), 3.2% (LDL cholesterol), and shifts in baseline from normal to low were reported in 13.3% (HDL cholesterol) of patients taking REXULTI plus ADT. Of patients with normal baseline triglycerides, 17.3% experienced shifts to high, and 0.2% experienced shifts to very high triglycerides. Combined, 0.6% of subjects with normal or borderline fasting triglycerides experienced shifts to very high fasting triglycerides during the long-term MDD studies.
Agitation Associated with Alzheimer’s Dementia (AAD)
In the 12-week placebo-controlled, fixed-dose and flexible-dose clinical studies in patients (51 to 90 years of age) with AAD (Trials 10, 11 and 12), changes in total cholesterol, LDL cholesterol, and HDL cholesterol were similar in patients treated with REXULTI and patients treated with placebo. Table 21 shows the proportions of subjects with changes in fasting triglycerides. Changes seen in fasting triglycerides from normal/borderline (<200 mg/dL) to very high (≥500 mg/dL) were similar in patients treated with REXULTI and patients treated with placebo.
Table 21: Change in Fasting Triglycerides in Trials 10, 11 and 12 (up to 12 weeks)
| Proportion of Subjects with Shifts Baseline to Post-Baseline | ||||||||
| Brexpiprazole (mg/day) | ||||||||
| Triglycerides | ≤1 mg/day1 | 2 mg/day2 | 3 mg/day2 | 2 and 3 mg/day | 0.5-2 mg/day3 | ALL | Placebo | |
Normal to High (<150 mg/dL to ≥200 and <500 mg/dL) | 8% (9/114)* | 13% (17/133)* | 6% (6/94)* | 10% (23/227)* | 6% (5/89)* | 9% (37/430)* | 8% (20/253)* | |
| Borderline to High (150 and <200mg/dL to 200 and <500 mg/dL) | 29% (2/7)* | 28% (7/25)* | 26% (6/23)* | 27% (13/48)* | 32% (7/22)* | 29% (22/77)* | 12% (5/41)* | |
| Normal/Borderline to High (<200 mg/dL to 200 and <500 mg/dL) | 9% (11/121)* | 15% (24/158)* | 10% (12/117)* | 13% (36/275)* | 11% (12/111)* | 12% (59/507)* | 9% (25/294)* | |
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
* denotes n/N where N=the total number of subjects who had a measurement at baseline and at least one post-baseline result.
n=the number of subjects with shift.
Patients (55 to 90 years of age) from the 12-week placebo-controlled, fixed-dose clinical study, who rolled over into a 12-week, active-treatment extension study, showed shifts in baseline fasting total cholesterol from normal (<200 mg/dL) to high (≥240 mg/dL) which were reported in 10% of patients taking REXULTI, and shifts in baseline HDL cholesterol from normal to low (≥ 40 to <40 mg/dL) which were reported in 14% of patients taking REXULTI. Of patients with normal baseline triglycerides, 12% experienced shifts from normal (<150 mg/dL) to high (200 to <500 mg/dL).
Prolactin
Schizophrenia
Table 22 shows the mean change from baseline in prolactin and the proportion of subjects with prolactin elevations.
Table 22: Changes in Prolactin (ng/mL) - Trials 1 and 2 (up to 6 weeks)
| Brexpiprazole (mg/day) | |||||
| 1 mg/day | 2 mg/day | 4 mg/day | Placebo | ||
| Mean Change from Baseline (ng/mL) at Last Visit | |||||
| All Male | N=73 | N=220 | N=208 | N=206 | |
| -2.16 | -1.36 | -0.47 | -1.08 | ||
| All Female | N=41 | N=129 | N=132 | N=127 | |
| -1.08 | -1.31 | -0.81 | -5.57 | ||
| Male with normal baseline | N=40 | N=139 | N=145 | N=142 | |
| +2.61 | +2.52 | +3.12 | +1.36 | ||
| Female with normal baseline | N=29 | N=102 | N=102 | N=92 | |
| +5.95 | +7.00 | +6.46 | +2.55 | ||
| Proportion of Subjects with new onset abnormal results at any time post-baseline | |||||
| All Male | N=73 | N=221 | N=208 | N=207 | |
| >1x ULN | 10% | 12% | 17% | 12% | |
| >2x ULN | 3% | 3% | 0.5% | 5% | |
| >3x ULN | 0% | 0% | 2% | 2% | |
| All Female | N=41 | N=129 | N=132 | N=127 | |
| >1x ULN | 7% | 12% | 17% | 7% | |
| >2x ULN | 7% | 6% | 3% | 5% | |
| >3x ULN | 2% | 1% | 1% | 2% | |
Legend: ULN = Upper Limits of Normal
In the longer-term randomized withdrawal Trial 3, the mean change from baseline at last visit in prolactin in females was -2.17 ng/mL in REXULTI-treated group compared with -4.25 ng/mL in the placebo group. In males, mean change from baseline at last visit in prolactin was -1.73 ng/mL in REXULTI-treated group compared with 1.38 ng/mL in the placebo group. For females with normal prolactin results at baseline, the mean changes to last visit were 4.04 ng/mL in the REXULTI-treated group and -5.95 ng/mL in the placebo group; for males with normal baseline, the mean changes to last visit were 0.05 ng/mL in the REXULTI-treated group and 2.61 ng/mL in the placebo group. The proportion of subjects with prolactin elevations >1X ULN in females was 5.2% in the REXULTI-treated group compared with 2.6% in the placebo group. In males, the proportion of subjects with prolactin elevations > 1X ULN was 3.6% in the REXULTI-treated group compared with 4.9% in the placebo group. Similarly, prolactin elevations >3X ULN in females was 0.0% in the REXULTI-treated group compared with 5.2% in the placebo group. In males, prolactin elevations >3X ULN was 0.0% in the REXULTI-treated group compared with 3.2% in the placebo group.
In the long-term open-label schizophrenia trials, the mean change from baseline at last visit in prolactin in females was 2.78 ng/mL in REXULTI-treated group and 0.60 ng/mL in males. The proportion of subjects with prolactin elevations >1X ULN was 17.5% in females and 14.0% in males in the REXULTI-treated group, and prolactin elevations >3X ULN was 4.1% in females and 1.7% in males.
Adjunctive Treatment in Major Depressive Disorder (MDD)
Table 23 shows the mean change from baseline in prolactin and the proportion of subjects with prolactin elevations in Trials 4, 5, 6 and 7.
Table 23: Changes in Prolactin (ng/mL) - Trials 4, 5, 6 and 7 (up to 6 weeks)
| Brexpiprazole (mg/day)+ADT | |||||||
| 1 mg/day | 2 mg/day | 3 mg/day | 2-3 mg/day1 | Placebo+ADT | |||
| Mean Change from Baseline (ng/mL) at Last Visit | |||||||
| All Male | N=68 | N=100 | N=72 | N=68 | N=235 | ||
| +0.98 | +2.16 | +2.14 | +0.26 | -0.01 | |||
| All Female | N=154 | N=262 | N=152 | N=122 | N=559 | ||
| +3.99 | +7.69 | +10.28 | +1.09 | +0.06 | |||
| Male with normal baseline | N=60 | N=97 | N=67 | N=60 | N=215 | ||
| +1.55 | +2.13 | +2.86 | +1.37 | +0.12 | |||
| Female with normal baseline | N=153 | N=254 | N=150 | N=115 | N=543 | ||
| +4.13 | +8.14 | +10.52 | +1.92 | +0.67 | |||
| Proportion of Subjects with new onset abnormal results at any time post-baseline | |||||||
| All Male | N=68 | N=102 | N=72 | N=68 | N=242 | ||
| >1x ULN | 18% | 15% | 22% | 19% | 9% | ||
| >2x ULN | 0% | 0% | 1% | 6% | 3% | ||
| >3x ULN | 0% | 1% | 1% | 2% | <1% | ||
| All Female | N=155 | N=270 | N=155 | N=123 | N=571 | ||
| >1x ULN | 10% | 17% | 26% | 11% | 3% | ||
| >2x ULN | 0% | 1% | 2% | 1% | <1% | ||
| >3x ULN | 0% | 0% | 0% | 2% | 1% | ||
Legend: ADT=antidepressant, ULN = Upper Limits of Normal
1Brex 2-3 mg/day group is from flexible-dose trial 7 (Trial 331-12-282)
In the long-term open-label MDD trials, the mean change from baseline at last visit in prolactin in females was 1.86 ng/mL in REXULTI plus ADT group and 0.50 ng/mL in males. The proportion of subjects with prolactin elevations >1X ULN was 15.4% in females and 13.5% in males in the REXULTI plus ADT group, and prolactin elevations >3X ULN was 0.5% in females and 0.9% in males.
Agitation Associated with Alzheimer’s Dementia (AAD)
Table 24 shows the mean change from baseline in prolactin and the proportion of subjects with prolactin elevations in Trials 10, 11 and 12.
Table 24: Changes in Prolactin (ng/mL) - Trials 10, 11, and 12 (up to 12 weeks)
| Brexpiprazole (mg/day) | |||||||||
| ≤1 mg/day1 | 2 mg/day2 | 3 mg/day2 | 2 and 3 mg/day | 0.5-2 mg/day3 | ALL | Placebo | |||
| Mean Change from Baseline (ng/mL) at Last Visit | |||||||||
| All Male | N=67 | N=88 | N=53 | N=141 | N=50 | N=258 | N=164 | ||
| -1.14 | -0.26 | +0.74 | 0.12 | 0.23 | -0.19 | -0.03 | |||
| All Female | N=89 | N=117 | N=78 | N=195 | N=80 | N=364 | N=207 | ||
| -0.47 | +0.98 | +1.91 | 1.35 | -3.80 | -0.22 | -4.62 | |||
| Proportion of Subjects with new onset abnormal results at any time post-baseline | |||||||||
| All Male | N=67 | N=88 | N=53 | N=141 | N=50 | N=258 | N=164 | ||
| >1x ULN | 15% | 23% | 6% | 16% | 4% | 14% | 9% | ||
| >2x ULN | 5% | 5% | 6% | 5% | 0% | 4% | 2% | ||
| >3x ULN | 9% | 1% | 0% | <1% | 0% | 3% | 3% | ||
| All Female | N=89 | N=117 | N=78 | N=195 | N=80 | N=364 | N=207 | ||
| >1x ULN | 6% | 5% | 9% | 7% | 4% | 6% | 3% | ||
| >2x ULN | 2% | 3% | 0% | 2% | 1% | 2% | 1% | ||
| >3x ULN | 1% | 0% | 0% | 0% | 0% | <1% | 1% | ||
1 Brex ≤1 mg/day group is from fixed-dose trial 10 (Trial 331-12-283)
2 Brex 2 mg/day and Brex 3 mg/day are from fixed-dose trial 10 and 11 (Trial 331-12-283 and Trial 331-14-213)
3 Brex 0.5-2 mg/day group is from flexible-dose trial 12 (Trial 331-12-284)
Legend: ULN = Upper Limits of Normal
In the 12-week, active-treatment extension trial, potentially clinically relevant high prolactin values were reported in 7 (5.0%) subjects who received prior brexpiprazole and 6 (6.9%) prior placebo subjects.
8.5 Post-Market Adverse Reactions
Immune system disorders: hypersensitivity reactions (including anaphylaxis, angioedema, facial swelling, rash and urticaria)
Neurological: seizure, neuroleptic malignant syndrome
Psychiatric disorders: suicidality (including completed suicide, attempted suicide, suicidal behaviour and suicidal ideation).
Atypical antipsychotic drugs, such as REXULTI, have been associated with cases of sleep apnea, with or without concomitant weight gain. In patients who have a history of or are at risk for sleep apnea, REXULTI should be prescribed with caution.
Complex sleep-related behaviours such as somnambulism and sleep-related eating disorder have been associated with the use of atypical antipsychotic drugs.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
REXULTI is predominantly metabolized by cytochrome P450 (CYP)3A4 and CYP2D6.
REXULTI should be used with caution in combination with drugs known to prolong QTc interval or cause electrolyte disturbances (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular, QT Interval).
9.3 Drug-Behavioural Interactions
Alcohol/CNS Drugs
Given the primary CNS effects of brexpiprazole, as with most psychoactive medications, combination use of REXULTI with alcohol or other CNS drugs with overlapping undesirable effects such as sedation, should be avoided.
Smoking
Based on studies utilizing human liver enzymes in vitro, brexpiprazole is not a substrate for CYP1A2. No dosage adjustment is required based on smoking status.
9.4 Drug-Drug Interactions
Potential for other drugs to affect REXULTI
Dosage adjustments are recommended in patients who are known CYP2D6 poor metabolizers and in patients taking concomitant CYP3A4 inhibitors or CYP2D6 inhibitors or strong CYP3A4 inducers (Table 25). If the co-administered drug is discontinued, adjust the REXULTI dosage to its original level. If the co-administered CYP3A4 inducer is discontinued, reduce the REXULTI dosage to the original level over 1 to 2 weeks (see 4.1 Dosing Considerations).
Table 25: Summary of Effect of Co-administered Drugs on Exposure to REXULTI (brexpiprazole) in Healthy Subjects
| Co-administered Drug | Ref | Dose Schedule Clinical comment | Effect on REXULTI Pharmacokinetics | Recommendation | |||||||||
| Co-administere d Drug | REXULTI | Cmax | AUC | ||||||||||
| Ketoconazole (strong CYP3A4 inhibitor*) | CT | 200 mg BID for 7 days | single 2 mg dose | No change | Increased by 97% | Administer half of usual REXULTI dose | |||||||
| Quinidine (strong CYP2D6 inhibitor) | CT | 324 mg OD for 7 days | single 2 mg dose | No change | Increased by 94% | Administer half of usual REXULTI dose | |||||||
| Ticlopidine (strong CYP2B6 inhibitor) | CT | 250 mg BID for 7 days | single 2 mg dose | No change | No change | No REXULTI dose adjustment required | |||||||
| Rifampin (strong CYP3A4 inducer) | CT | 600 mg BID for 12 days | single 4 mg dose | Decreased by 31% | Decreased by 73% | Double usual REXULTI dose over 1 to 2 weeks, adjust as required based on clinical response | |||||||
| Omeprazole (Gastric Acid pH Modifiers) | CT | 40 mg OD for 5 days | single 4 mg dose | No change | No change | No REXULTI dose adjustment required | |||||||
Legend: CT = Clinical Trial, Cmax = Maximum Concentration, AUC = Area Under the Curve
*Mild and moderate CYP3A4 inhibitors (e.g. erythromycin, grapefruit juice) have not been studied
The effects of other drugs on the exposure of REXULTI are summarized in Figure 1.
Figure 1: The Effects of Other Drugs on REXULTI (brexpiprazole) Pharmacokinetics*
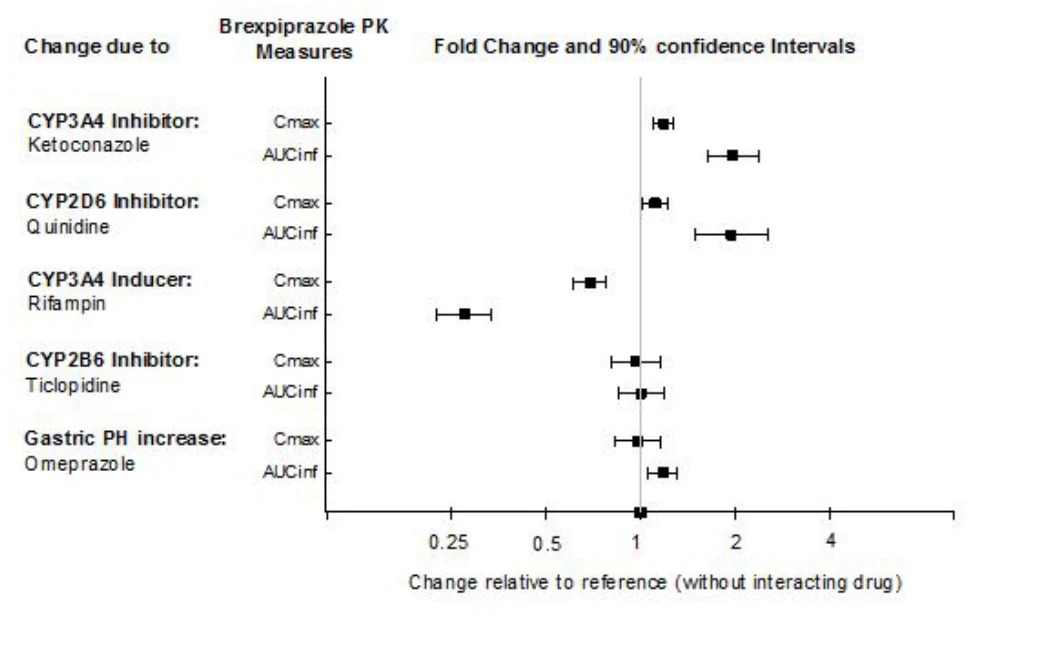
*see also impact for dosage recommendations in Table 25 above.
Potential for REXULTI to affect other drugs
Results of in vitro studies suggest that REXULTI is unlikely to cause clinically important pharmacokinetic interactions with drugs metabolized by cytochrome P450 enzymes. Clinical studies showed that oral brexpiprazole (2 mg/day, 5 days) had no effect on the metabolism of single doses of dextromethorphan (a CYP2D6 substrate), lovastatin (a CYP3A4 substrate) or bupropion (a CYP2B6 substrate). REXULTI did not affect absorption of single doses of drugs that are substrates of BCRP transporter (rosuvastatin) and PgP (P-glycoprotein) transporter (fexofenadine). No dosage adjustment of CYP2D6, CYP3A4, CYP2B6, BCRP and PgP substrates is required during concomitant administration with REXULTI.
The effects of REXULTI on the exposure of other drugs are summarized in Figure 2.
Figure 2: The Effects of REXULTI (brexpiprazole) on Pharmacokinetics of Other Drugs
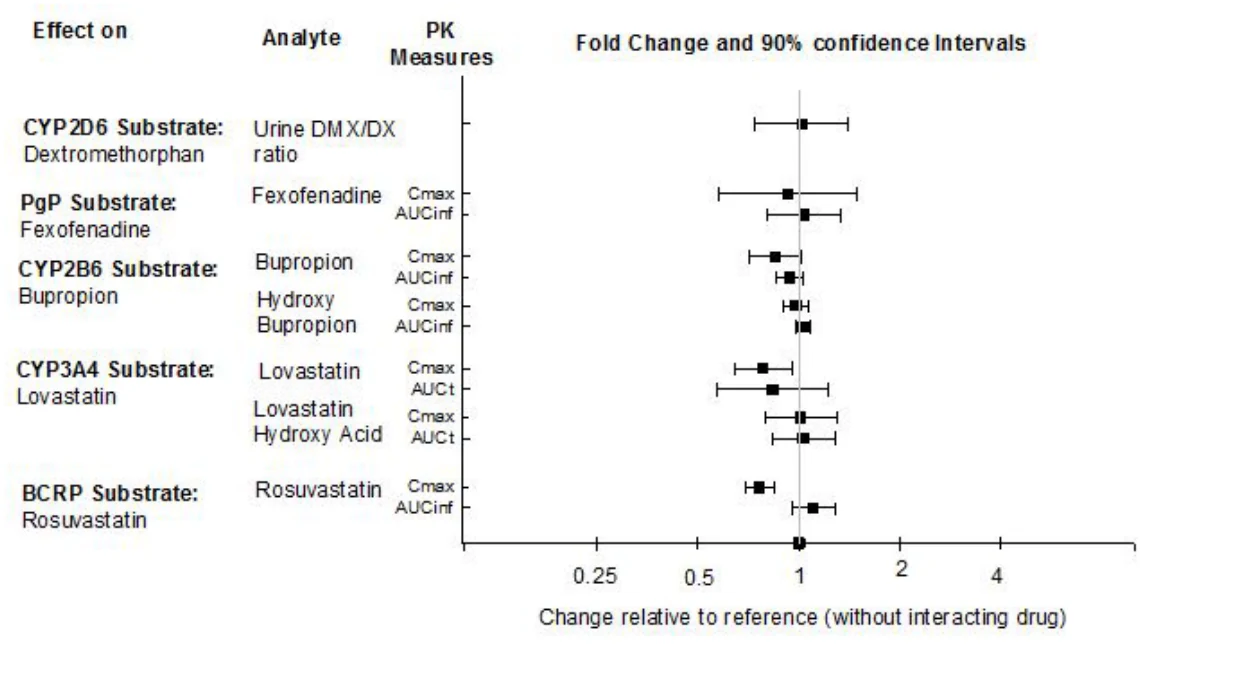
9.5 Drug-Food Interactions
REXULTI may be administered with or without food.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The mechanism of action of brexpiprazole is unknown. The efficacy of brexpiprazole may be mediated through a combination of partial agonist activity at serotonergic 5-HT1A and at dopaminergic D2 receptors with antagonist activity at serotonergic 5-HT2A receptors. The clinical relevance of these receptor interactions with brexpiprazole is unknown.
10.2 Pharmacodynamics
Brexpiprazole has high affinity (expressed as Ki values) for serotonin 5HT1A (0.12 nM), 5HT2A (0.47 nM), 5HT2B (1.88 nM), dopamine D2 (0.3 nM), D3 (1.14 nM), and noradrenergic α1A (3.78 nM), α1B (0.17 nM), α1D (2.60 nM), and α2C (0.59 nM) receptors.
Brexpiprazole exhibits a moderate affinity for dopamine D4 (6.3 nM), serotonin 5-HT7A (9.48 nM), noradrenergic α2A (15 nM), α2B (17 nM) and histamine H1 (19 nM) receptors; and weak affinity for the serotonin 5-HT1B (32 nM) and 5-HT2C (33 nM) receptors.
Brexpiprazole acts as a partial agonist at the 5-HT1A, D2, and D3 receptors and as an antagonist at 5HT2A, 5HT2B, 5HT7, α1A, α1B, α1D, and α2C receptors.
Cardiac Electrophysiology: In a multicenter, randomized, double-blind, placebo- and positive-controlled, parallel group, multiple dose ECG assessment study, subjects with schizophrenia or schizoaffective disorder received treatment with brexpiprazole at a therapeutic dose of 4 mg/day or a supratherapeutic dose of 12 mg/day for 11 days. On day 11, the maximum placebo-adjusted mean change from baseline in the QTcI interval was 8.3 ms (90% CI 3.7, 12.9) at 6 h post-dosing in the brexpiprazole 4 mg/day group (N=62) and 3.1 ms (90% CI -1.7, 8.0) at 4 h post-dosing in the brexpiprazole 12 mg/day group (N=53). No exposure-response relationship was apparent.
Sub-group analyses suggested that the QTc prolongation was larger in female subjects than in males. In the brexpiprazole 4 mg/day group, the maximum placebo-adjusted mean change from baseline in the QTcI interval was 5.2 ms (90% CI 1.5, 8.9) in males (N=48) and 15.0 ms (90% CI 7.7, 22.3) in females (N=14) at 6 h post-dosing. In the brexpiprazole 12 mg/day group, the maximum placebo-adjusted mean change from baseline in the QTcI interval was 2.9 ms (90% CI -1.2, 6.9) in males (N=40) at 12 h post-dosing and 10.4 ms (90% CI 2.7, 18.2) in females (N=13) at 24 h post-dosing. Limitations of the sex sub-group analyses included diminished statistical power.
The brexpiprazole 4 mg/day treatment had no effect on heart rate; however, the brexpiprazole 12 mg/day treatment was associated with an increase in heart rate, with a maximum mean difference from placebo of 4.8 bpm (90% CI 1.9, 7.7) at 2 h.
10.3 Pharmacokinetics
Absorption: After single dose administration of REXULTI tablets, the peak plasma brexpiprazole concentrations occurred within 4 hours after administration; and the absolute oral bioavailability was 95%. Brexpiprazole steady-state concentrations were attained within 10-12 days of dosing.
REXULTI can be administered with or without food. Administration of a 4 mg REXULTI tablet with a standard high-fat meal did not significantly affect the Cmax or AUC of brexpiprazole. After single and multiple once daily dose administration, brexpiprazole exposure (Cmax and AUC) increased in proportion to the dose administered. In vitro studies of brexpiprazole did not indicate that brexpiprazole is a substrate of efflux transporters such as MDRI (P-gp) and BCRP.
Distribution: The volume of distribution of brexpiprazole following intravenous administration is high (1.56±0.42 L/kg), indicating extravascular distribution. Brexpiprazole is highly protein bound in plasma (greater than 99%) to serum albumin and α1-acid glycoprotein, and its protein binding is not affected by renal or hepatic impairment. Based on results of in vitro studies, brexpiprazole protein binding is not affected by warfarin, diazepam, or digitoxin.
Metabolism: Based on in vitro metabolism studies of brexpiprazole using recombinant human cytochrome P450 (CYP1A1, 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, and 3A4), the metabolism of brexpiprazole was shown to be mainly mediated by CYP3A4 and CYP2D6. Based on in vitro data, brexpiprazole showed little to no inhibition of CYP450 isozymes.
In vivo brexpirazole is metabolized primarily by CYP3A4 and CYP2D6 enzymes. After single- and multiple-dose administrations, brexpiprazole and its major metabolite, DM-3411, were the predominant drug moieties in the systemic circulation. At steady-state, DM-3411 represented 23% to 48% of brexpiprazole exposure (AUC) in plasma. DM-3411 is considered not to contribute to the therapeutic effects of brexpiprazole.
Elimination: Following a single oral dose of [14C]-labeled brexpiprazole, approximately 25% and 46% of the administered radioactivity was recovered in the urine and feces, respectively. Less than 1% of unchanged brexpiprazole was excreted in the urine and approximately 14% of the oral dose was recovered unchanged in the feces. Apparent oral clearance of brexpiprazole oral tablet after once daily administration is 19.8 (±11.4) mL/h/kg. After multiple once daily administration of brexpiprazole, the terminal elimination half-life of brexpiprazole and its major metabolite, DM-3411, is 91.4 hours and 85.7 hours, respectively.
Special Populations and Conditions
Pediatrics: The safety and efficacy of REXULTI in patients under the age of 18 years have not been established.
The pharmacokinetics, safety and tolerability of brexpiprazole 0.5 - 4 mg per day oral doses were assessed in 43 adolescent subjects (aged 13 to 17 years, weight range 43.4 - 116.2 kg) with a diagnosis of schizophrenia, bipolar disorder, or other related psychiatric disorders in an open-label, dose-escalation trial (Trial 8). The brexpiprazole exposure, in terms of AUC and Cmax, seemed slightly higher and apparent clearance seemed slightly lower in adolescent subjects compared with adult subjects.
The pharmacokinetics, safety and tolerability of brexpiprazole single oral doses of 0.75 and 1.5 mg in 12 subjects 6 to < 10 years old (weight range 20.1 - 40.0 kg) and single oral doses of 1.5 and 3 mg in 12 subjects 10 to < 13 years old (weight range 28.0 - 61.0 kg) with a diagnosis of CNS disorders were assessed in a sequential cohort, nonrandomized crossover trial (Trial 9). Children 6 to < 10 years old appeared to have slightly higher brexpiprazole exposure and lower brexpiprazole apparent clearance as compared to children 10 to < 13 years old.
The pharmacokinetic profile in pediatric patients and the comparison with adults should be considered preliminary. REXULTI is not indicated for use in patients below the age of 18 (see 1.1 Pediatrics; 7.1.3 Pediatrics).
Geriatrics: Clinical studies for the treatment of schizophrenia and MDD in patients treated with REXULTI did not include a meaningful number of subjects aged 65 or older to determine whether they respond differently from younger adult patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, and cardiac function, concomitant diseases, and other drug therapy.
Antipsychotic drugs increase the risk of death in elderly patients with dementia (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
CYP2D6 Poor Metabolism Status: Based on the results of the population PK analysis CYP2D6 poor metabolizer subjects exhibited 47% higher exposure (AUCτ) to brexpiprazole compared with CYP2D6 extensive metabolizer subjects (see 4.1 Dosing Considerations).
Age/Sex: After single dose administration of brexpiprazole (2 mg), elderly subjects (older than 65 years old) exhibited similar brexpiprazole systemic exposure (Cmax and AUC) in comparison to the adult patients (18-45 years old) and female subjects exhibited approximately 40-50% higher brexpiprazole systemic exposure (Cmax and AUC) in comparison to the male subjects. Population pharmacokinetic evaluation identified age and female sex as statistically significant covariates affecting brexpiprazole PK while the effects were not considered clinically relevant. No dosage adjustment is required in subjects based on age or sex (see 7.1.4 Geriatrics).
Ethnic Origin: Although no specific pharmacokinetic study was conducted to investigate the effects of race on the disposition of brexpiprazole, population pharmacokinetic evaluation revealed no evidence of clinically significant race-related differences in the pharmacokinetics of brexpiprazole. No dosage adjustment is required in patients based on race.
Hepatic Insufficiency: In subjects with varying degrees of hepatic impairment (Child-Pugh Classes A, B, and C; N=22), the AUC of oral brexpiprazole (2 mg single dose), compared to matched healthy subjects, increased 24% in mild hepatic impairment, increased 60% in moderate hepatic impairment, and 8% in severe hepatic impairment. Specific dosing considerations are recommended for patients with moderate to severe hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment).
Renal Insufficiency: In subjects with severe renal impairment (CLcr <30 mL/min; N=10), AUC of oral brexpiprazole (2 mg single dose) compared to matched healthy subjects was increased by 68% while its Cmax was not changed. Specific dosing considerations are recommended for patients with moderate, severe or end stage renal impairment (see 4.2 Recommended Dose and Dosage Adjustment, Renal Impairment).
11 STORAGE, STABILITY AND DISPOSAL
Store REXULTI tablets between 15°- 30°C (59°- 86°F).
12 SPECIAL HANDLING INSTRUCTIONS
Keep out of reach and sight of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: brexpiprazole
Chemical name: 7-{4-[4-(1-Benzothiophen-4-yl)piperazin-1-yl]butoxy}quinolin-2(1H)-one
Molecular formula and molecular mass: C25H27N3O2S
433.57g/mol.
Structural formula:
Physicochemical properties: Brexpiprazole is nonhygroscopic, with white to off white crystals or crystalline powders, and a melting point of 183°C (decomposition). Brexpiprazole is a weakly basic compound with a pKa of 7.8. It is practically insoluble in water, and the solubility of the drug substance at pH 2 is 0.56 mg/mL, at pH 4 is 0.13 mg/mL, and at pH 6 is 0.0020 mg/mL.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Schizophrenia
The efficacy of REXULTI (brexpiprazole tablets) in the treatment of adults with schizophrenia was demonstrated in two 6-week, randomized, double-blind, placebo-controlled fixed-dose clinical trials and one longer-term randomized withdrawal trial in subjects who met Diagnostic and Statistical Manual of Mental Disorders (DSM-IV-TR) criteria for schizophrenia and were experiencing an acute exacerbation of psychotic symptoms. The efficacy was also evaluated in a 6-week, randomized, double-blind, placebo-controlled and active-reference flexible-dose clinical trial.
In two fixed-dose trials, Trial 231 (hereafter “Trial 1”) and Trial 230 (hereafter “Trial 2”), subjects were randomized to REXULTI 2 or 4 mg once per day or placebo. Subjects in the REXULTI groups initiated treatment at 1 mg once daily on Days 1 to 4. The REXULTI dosage was increased to 2 mg on Days 5 to 7. The dosage was then either maintained at 2 mg once daily or increased to 4 mg once daily, depending on treatment assignment, for the 5 remaining weeks. The primary efficacy endpoint of both trials was the change from baseline to Week 6 in the Positive and Negative Syndrome Scale (PANSS) total score. The PANSS is a 30-item scale that measures positive symptoms of schizophrenia (7 items), negative symptoms of schizophrenia
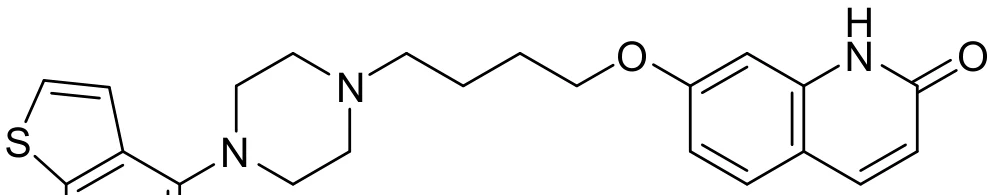
(7 items), and general psychopathology (16 items), each rated on a scale of 1 (absent) to 7 (extreme); the total PANSS scores range from 30 (best) to 210 (worst). The key secondary endpoint of both trials was the change from baseline to Week 6 in Clinical Global Impression Severity of Illness Scale (CGI-S) total score, a validated clinician-related scale that measures the subject’s current illness state and overall clinical state on a 1 (normal, not at all ill) to 7-point (extremely ill) scale.
The longer term Trial 3 was a randomized-withdrawal, double-blind, placebo-controlled trial to assess the efficacy of REXULTI (1 - 4 mg/day) in adults with schizophrenia experiencing an exacerbation of psychotic symptoms at study entry, who met criteria for stability for at least 12 weeks during single-blind treatment with REXULTI (flexible doses 1- 4 mg/day), and were then randomized to continue on their REXULTI dose or to switch to placebo, for up to 52 weeks. The primary endpoint was the time to exacerbation of psychotic symptoms/impending relapse; the key secondary endpoint was the percentage of subjects with exacerbation of psychotic symptoms/impending relapse.
Study Results
In Trial 1, REXULTI was superior to placebo (N=178) at both 2 mg/day (n=180) and 4 mg/day (N=178) doses for the primary endpoint (PANSS total score) and key secondary endpoint (CGI-S total score).
In Trial 2, REXULTI at 4 mg/day group (N=181) was superior to placebo (N=180) for the primary endpoint (PANSS total score), but not at the 2 mg/day dose (N=179).
Examination of population subgroups based on age, sex and race did not suggest differential responsiveness.
In the 6-week flexible-dose study (Study 14644A), REXULTI at doses between 2 and 4 mg/day (N=150) was not superior to placebo (N=159) for the primary endpoint, the mean changes in PANSS total score at Week 6; however, the active reference (N=150) confirmed the assay sensitivity of the study.
In the longer-term Trial 3, pre-specified interim analysis, conducted after 50% of the events planned in the calculation of power, demonstrated a statistically significantly longer time to relapse in subjects randomized to the REXULTI group compared to placebo-treated subjects and the trial was subsequently terminated early because of demonstrated efficacy. The final analysis demonstrated a statistically significantly longer time to relapse in subjects randomized to the REXULTI group (N=96) compared to placebo-treated subjects (N=104). Time to impending relapse was statistically significantly delayed with REXULTI compared with placebo in both the interim and final analyses (p = 0.0008 and p < 0.0001, respectively; log-rank test). For the final analysis, the hazard ratio from the Cox proportional hazard model for the placebo to REXULTI comparison was 3.420 (95% CI: 1.825, 6.411); thus, subjects in the placebo group had a 3.4-fold greater risk of experiencing impending relapse than the subjects in the REXULTI group.
The key secondary endpoint of Trial 3, the proportion of subjects who met the criteria for impending relapse, was statistically significantly lower in REXULTI-treated subjects compared with placebo group (13.5% versus 38.5%, p<0.0001).
Adjunctive Treatment in Major Depressive Disorder (MDD)
The efficacy of REXULTI, as an adjunctive treatment to antidepressant therapy for major depressive disorder (MDD), was evaluated in four phase 3, 6-week, double-blind, placebo-controlled trials: three fixed-dose trials (331-10-228, 331-10-227, 331-13-214) and one flexible-dose trial with an active reference (331-12-282). These trials are referred to as Trials 4, 5, 6 and 7, respectively, in Table 26.
The adult patients in these trials fulfilled the DSM-IV-TR criteria for MDD, with or without symptoms of anxiety, and demonstrated an inadequate response (patient reported) to 1-3 prior antidepressant therapy(ies) in the current episode and an inadequate response during the 8-10 weeks of prospective antidepressant treatment (escitalopram, fluoxetine, paroxetine controlled-release, sertraline, duloxetine or venlafaxine extended-release) during the trials. Inadequate response to prospective antidepressant treatment in Trials 4 and 5 was initially defined as < 50% improvement from baseline on the Hamilton Depression scale (HAMD-17), a HAMD-17 score ≥ 14, and a Clinical Global Impression (CGI-I) ≥ 3 at Week 8. To ensure that randomized patients had an inadequate response throughout the prospective antidepressant treatment phase, this definition was amended during Trials 4 and 5 to the following: < 50% improvement from baseline on the HAMD-17 and a HAMD-17 score ≥ 14 at Week 8; and, CGI-I ≥ 3 and < 50% improvement from baseline on the Montgomery-Asberg Depression Rating Scale (MADRS) Total Score at Weeks 2, 4, 6 and 8 (and Week 10, as applicable). This definition of inadequate response to prospective antidepressant treatment was also applied in Trial 6. With the exception of approximately 6% of patients in Trials 4 and 5, all patients who were randomized in the short-term clinical trials 4, 5, and 6 fulfilled the revised definition of inadequate response to prospective antidepressant treatment. In Trial 7, as the HAMD-17 was not administered, a MADRS total score ≥18 at the end of prospective treatment was used in lieu of HAMD-17 score ≥14.
Patients remained on the same antidepressant treatment throughout the entire duration of each study. All patients randomized to REXULTI in the fixed-dose studies (Trials 4, 5 and 6) initiated treatment at 0.5 mg/day during Week 1. The REXULTI dose was increased to 1 mg/day during Week 2 in all dose groups and, based on the assigned treatment, the dose was either maintained at 1 mg/day or increased to 3 mg/day (Trial 5) or increased to 2 mg/day (Trials 4 and 6), from Week 3 onwards. Dosages were maintained at the assigned doses for the 4 remaining weeks. In the flexible-dose study (Trial 7), patients randomized to REXULTI initiated treatment at 1 mg/day during Week 1, and the dose was increased to the target dose of 2 mg/day during Week 2. Patients remained at 2 mg/day in Trial 7 unless there was a decision to increase the dose to 3 mg/day.
The primary efficacy endpoint in all studies was mean change from baseline (randomization) to Week 6 on the Montgomery Asberg Depression Rating Scale (MADRS) Total Score, a 10-item clinician-rated scale that assesses the degree of depressive symptomatology (apparent sadness, reported sadness, inner tension, reduced sleep, reduced appetite, concentration difficulties, lassitude, inability to feel, pessimistic thoughts, and suicidal thoughts). Each item is scored from 0 (normal/symptom not present) to 6 (most severe symptoms) and the range for the total score is 0 to 60.
The key secondary instrument was the Sheehan Disability Scale (SDS), a 3-item self-rated instrument used to assess three domains of functioning (work/school, social life, and family life) with each item scored from 0 (no disruption at all) to 10 (extreme disruption).
Table 26: Clinical Trials Supporting Efficacy of REXULTI in the Adjunctive Treatment in Major Depressive Disorder
| Study | Trial designa | Oral Dosage | Number of Subjects (N)b Sex [Male/Female (M/F)]b | Age (yrs) Mean (SD)b |
| 331-10-228 (Trial 4) | Phase A (8 weeks): Single-blind placebo +ADT Phase B (6 weeks): Double-blind, placebo-controlled + ADT | 2 mg/day Brex+ADT | N=187 (58M/129F) | 44.1 (11.6) |
| Placebo+ADT | N=191 (54M/137F) | 45.2 (11.3) | ||
| 331-10-227 (Trial 5) | 1 mg/day Brex+ADT | N=225 (67M/158F) | 45.7 (11.6) | |
| 3 mg/day Brex+ADT | N=226 (71M/155F) | 44.6 (11.2) | ||
| Placebo+ADT | N=218 (75M/143F) | 46.6 (11.1) | ||
| 331-13-214 (Trial 6) | 2 mg/day Brex+ADT | N=191 (45M/146F) | 43.2 (12.6) | |
| Placebo+ADT | N=202 (58M/144F) | 42.7 (12.5) | ||
| 331-12-282 (Trial 7) | Phase A (8-10 weeks): Double-blind placebo +ADT Phase B (6 weeks): Double-blind, placebo-controlled and active-referenced + ADT | 2 to 3 mg/day Brex+ADT | N=191 (68M/123F) | 43.8 (11.5) |
| Placebo+ADT | N=205 (56M/149F) | 41.8 (11.7) | ||
Brex=brexpiprazole; ADT=antidepressant; SD=standard deviation
aThese were 14-16-week trials which required a retrospective failure to 1 to 3 courses of ADT treatment during the current depressive episode and consisted of an 8-10-week, single- or double-blind placebo plus ADT (Phase A), followed by a 6-week double-blind, randomization phase.
bDemographic characteristics based on randomized subjects (Phase B) who took at least one dose of study medication during Phase B and who had MADRS Total Score values at the randomization visit and at least one post-randomization visit.
Study Results
For the randomized patients in Trials 4-7, the mean duration of the current major depressive episode ranged between approximately 12 and 18 months and the majority of patients (approximately 79% - 84%) reported an inadequate response to one prior antidepressant treatment, before receiving 8-10 weeks of prospective antidepressant treatment during the trials. Following 8-10 weeks of prospective antidepressant treatment, the mean MADRS Total Score at randomization ranged between 25 and 27. Mean SDS score at randomization was between 5.6 and 6.3.
In Trials 4, 6 and 7 there was greater improvement in the mean MADRS Total Score with REXULTI (2 mg/day or 2-3 mg/day) plus ADT compared to placebo plus ADT (p < 0.05). No additional benefit was demonstrated at doses greater than 2 mg/day (Table 27). In Trial 7 the majority of patients treated with REXULTI received 2 mg/day and the mean daily REXULTI dose at endpoint was 2.2 mg/day.
| Table 27: Summary of the Primary Efficacy Results (MADRS) of REXULTI in Trials 4, 5, 6, and 7 for the Adjunctive Treatment in Major Depressive Disorder | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Trial Treatment Group | N | Baseline End of Phase A | Mean Change End of Phase B | Treatment Comparison versus Placebo | ||||||||||||||||
| Mean (SD) | LS Mean (SE)a | LSMDb | 95% CI a | P-valuea | ||||||||||||||||
| Trial 4c | ||||||||||||||||||||
| 2 mg Brex+ADT | 187 | 26.61 (5.79) | -8.27 (0.61) | -3.12 | (-4.70, -1.54) | 0.0001 | ||||||||||||||
| Placebo+ADT | 191 | 27.14 (5.60) | -5.15 (0.63) | - | - | - | ||||||||||||||
| Trial 5c | ||||||||||||||||||||
| 1 mg Brex+ADT | 225 | 26.69 (5.61) | -7.65 (0.50) | -1.19 | (-2.58, 0.20) | 0.0925 | ||||||||||||||
| 3 mg Brex+ADT | 226 | 26.31 (5.24) | -7.98 (0.51) | -1.52 | (-2.92, -0.13) | 0.0327 | ||||||||||||||
| Placebo+ADT | 218 | 26.23 (5.27) | -6.45 (0.51) | - | - | - | ||||||||||||||
| Trial 6 | ||||||||||||||||||||
| 2 mg Brex+ADT | 191 | 27.05 (5.67) | -10.4 (0.63) | -2.30 | (-3.97, -0.62) | 0.0074 | ||||||||||||||
| Placebo+ADT | 202 | 26.20 (6.20) | -8.07 (0.61) | - | - | - | ||||||||||||||
| Trial 7 | ||||||||||||||||||||
| 2-3 mg Brex+ADT | 191 | 25.28 (5.02) | -6.04 (0.43) | -1.48 | (-2.56, -0.39) | 0.0078 | ||||||||||||||
| Placebo+ADT | 205 | 25.39 (5.19) | -4.57 (0.41) | - | - | - | ||||||||||||||
Legend: ADT=antidepressant
NOTE: Baseline equals Week 8 or Week 10 measurement prior to randomization.
aMMRM with model terms treatment, site, visit, treatment-by-visit, and baseline-by-visit interaction as covariates, where baseline is MADRS Total Score at end of Phase A (Week 8). An unstructured covariance was used. To control Type 1 error for testing two doses in Trial 5, the brexpiprazole versus placebo treatment difference was statistically significant only if the larger of the two p-values was <0.05 or the smaller p-value was <0.025.
bLSMD was the difference between LS mean of brexpiprazole and placebo.
cResults for the primary analysis populations for Trials 4 and 5 are presented and include approximately 6% of patients who were randomized prior to the revised definition of inadequate response, which required an inadequate response throughout the 8-week duration of prospective antidepressant treatment.
In Trial 4, the mean SDS score showed greater improvement with REXULTI (2 mg/day) plus ADT than with placebo plus ADT (p<0.05).
Agitation Associated with Alzheimer’s Dementia (AAD)
The efficacy of REXULTI in the treatment of agitation associated with Alzheimer’s dementia (AAD) was evaluated in three 12-week, randomized, double-blind, placebo-controlled trials; two of which were fixed-dose trials (331-12-283 and 331-14-213, referred as Trials 10 and 11, respectively) and one was a flexible-dose trial (331-12-284, referred as Trial 12) in patients who met a diagnosis of probable Alzheimer’s disease according to National Institute of Neurological and Communicative Disorders and Stroke and the Alzheimer’s Disease and Related Disorders Association (NINCDS-ADRDA) criteria and a Mini-Mental State Examination (MMSE) score of ≥5 and ≤22. At entry, patients were required to have a total score of ≥4 on the agitation/aggression item of the Neuropsychiatric Inventory/Neuropsychiatric Inventory Nursing Home (NPI/NPI-NH). Patients were required to be exhibiting sufficient agitation behaviours at time of entry to warrant use of pharmacotherapy, after excluding other factors. In Trial 11, patients had also to meet the criteria for Cohen-Mansfield Agitation Inventory (CMAI) Factor 1 which represents aggressive behaviours. In order to meet this criterion, one of the following must be displayed: 1) ≥ 1 aggressive behaviours occurring several times per week, or 2) ≥ 2 aggressive behaviours occurring once or twice per week, or ≥ 3 aggressive behaviours occurring less than once per week.
The CMAI is a clinician-rated questionnaire consisting of 29 items, which assess the frequency of manifestations of agitated behaviours in elderly patients, based on caregiver input. Three specific factors can be derived from the CMAI scale: Factor 1) Aggressive Behaviour (e.g., screaming, throwing things, cursing/verbal aggression, kicking, pushing, scratching, hurting self or others); Factor 2) Physically Non-Aggressive Behaviour (e.g., repetitive mannerisms, general restlessness, pacing); and Factor 3) Verbally Agitated Behaviour (e.g., complaining, repetitive questions, constant requests for attention). Each CMAI behaviour was rated on a scale of 1 (never) to 7 (very frequent agitated behaviours); the total CMAI scores range from 29 (best) to 203 (worst). A negative change in score indicates improvement.
Trial 10 included 433 patients with a mean age of 74 years, and a range of 51 and 90 years. Trial 11 included 345 patients with a mean age of 74 years, and a range of 56 and 90 years.
Trial 12 included 270 patients with a mean age of 74 years, and a range of 55 and 90 years.
The primary efficacy endpoint in all studies was the change from baseline in the CMAI score at Week 12. The key secondary efficacy endpoint was assessed by measuring the change from baseline in the Clinical Global Impression Severity (CGI-S) Scale score at the same time point.
Study Results
Patients in Trial 10 were randomized to a fixed dose of either REXULTI 1 mg once a day, 2 mg once a day or placebo. In this trial, patients who received REXULTI 2 mg once daily showed statistically significantly improved CMAI scores compared to patients who received placebo at Week 12. The once daily 1 mg dose did not demonstrate significantly greater mean changes at baseline from placebo in the CMAI score in this patient population (Table 28).
Patients in Trial 11 were randomized to a fixed dose of either REXULTI 2 mg once a day or 3 mg once a day (combined treatment arm) or placebo. In this trial, patients who received REXULTI 2 mg or 3 mg once daily showed statistically significantly improved CMAI and CGI-S scores compared to patients who received placebo at Week 12 (Table 28).
Patients in Trial 12 were randomized to a flexible dose ranging from 0.5 to 2 mg once a day or placebo. In this trial, patients who received REXULTI did not show a statistically significant improvement compared to patients who received placebo at Week 12 (Table 28).
It may take up to six to eight weeks after REXULTI initiation to demonstrate significant clinical efficacy.
| Table 28: Change in CMAI Total Score from Baseline at Week 12 in Patients with Agitation Associated with Alzheimer’s Dementia in Trials 10, 11, and 12 | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Trial Treatment Group | N | Mean Baseline Score (SD) | LS Mean Change (SE) | Treatment Difference* | |||||||||||||||
| LSMD | 95% CI | P-value | |||||||||||||||||
| Trial 10 | |||||||||||||||||||
| 1 mg Brex | 134 | 70.5 (16.0) | -17.6 (1.3) | 0.2 | (-3.4, 3.9) | 0.9015 | |||||||||||||
| 2 mg Brex† | 138 | 71.0 (16.6) | -21.6 (1.3) | -3.8 | (-7.4, -0.2) | 0.0404 | |||||||||||||
| Placebo | 131 | 72.2 (17.9) | -17.8 (1.3) | - | - | - | |||||||||||||
| Trial 11 | |||||||||||||||||||
| 2 or 3 mg Brex† | 225 | 80.6 (16.6) | -22.6 (1.1) | -5.3 | (-8.8, -1.9) | 0.0026 | |||||||||||||
| Placebo | 116 | 79.2 (17.5) | -17.3 (1.4) | - | - | - | |||||||||||||
| Trial 12 | |||||||||||||||||||
| 0.5 mg-2 mg Brex | 131 | 71.5 (16.8) | -18.9 (1.2) | -2.3 | (-5.5, 0.8) | 0.1454 | |||||||||||||
| Placebo | 135 | 68.6 (16.0) | -16.5 (1.1) | - | - | - | |||||||||||||
Legend: SD=standard deviation; SE=standard error; LS Mean=least-square mean; CI=unadjusted confidence interval
NOTE: *Difference (drug minus placebo) in least-squares mean change from baseline
†Dosages statistically significantly superior to placebo
In Trial 11, the mean change from baseline in the CGI-S score after 12 weeks in patients treated with 2 mg per day or 3 mg per day of REXULTI was statistically significantly superior to placebo (LSMD = −0.27, p = 0.0078).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Acute Toxicity
In single-dose oral (gavage) toxicity studies, the minimum oral lethal dose was >1000 and 300 mg/kg, respectively for male and female Sprague Dawley (SD) rats, and >100 mg/kg for both male and female cynomolgus monkeys. At doses of 1000 and 300 mg/kg, clinical signs observed in male and female rats included hypoactivity, closed eyes or incomplete eyelid closure, fixed stare, lacrimation, abnormal posture, and hypothermia. In monkey, clinical signs included drowsiness, partially closed eyes, crouching or prone positions, tremors of the limbs, decrease in movement, and decrease in body temperature.
Repeat Dose Toxicity
In a repeat-dose toxicity study conducted in rats at oral doses of 0, 3, 10, 30 and 100 mg/kg/day for 26 weeks duration, the no observed adverse effect level (NOAEL) was 3 mg/kg (7-fold MRHD on a mg/m2 basis). Clinical signs observed at 30 and 100 mg/kg included CNS depression, hypoactivity, hypothermia, gynecomastia, galactorrhea, and increases in blood levels of aspartate aminotransferase and gamma globulin, as well as decrease in body weight and food consumption. Female rats increased in body weight at 3 mg/kg compared to the control group. Major histopathology finding corresponded to atrophy of the uterus, thymus and pituitary glands, and enlargement of adrenal glands at doses ≥10 mg/kg.
In repeat-dose toxicity studies conducted in Cynomolgus monkeys at oral doses of 0, 1, 3 and 30 mg/kg/day for 13 and 39 weeks duration, the NOAEL was 1 mg/kg (5-fold MRHD) for both sexes. At doses ≥3 mg/kg, animals exhibited CNS depression, decrease in blood pressure, decreases in leukocytes and reticulocytes, as well as increases in blood cholesterol and phospholipids. Major histopathology finding corresponded to death-related gastrointestinal bleeding and ulcers at 30 mg/kg.
Brexpiprazole caused a decreased body temperature in repeat-dose toxicity studies at doses ≥30 mg/kg in rats, monkeys and dogs.
Significant decrease in blood pressure and prolongation of QT interval and QTc were noted in the conscious telemetry dog trial, and on Day 1 of administration at doses ≥ 3 mg/kg in the repeat-dose toxicity studies with monkeys and in the juvenile toxicity study with dogs (15- and 24-fold the MRHD on a mg/m2 basis, respectively). In conscious telemetry dogs (N=4), brexpiprazole was administered at sequential oral doses of 0 (vehicle), 1, 3, 10, and 30 mg/kg at intervals of 7-8 days. Brexpiprazole at 10 mg/kg and 30 mg/kg caused statistically significant increases in the QTc interval and the QRS duration compared to the vehicle control group.
Juvenile Repeat Dose Toxicity
In repeat-dose toxicity study conducted in juvenile rats at oral doses of 0, 3, 10 and 20 mg/kg/day for 8 weeks duration, the NOAEL was <3 mg/kg (7-fold MRHD on a mg/m2 basis) in both sexes. At doses ≥10mg/kg, animals exhibited CNS depression, hypoactivity, as well as increases in blood globulins and phospholipids. Decrease in body weight, pubertal delays and gynecomastia were also noted at the end of the administration period compared with the control group. Female rats increased in body weight at 3 mg/kg. Major histopathology finding corresponded to atrophy of the pituitary glands, liver and kidney at doses ≥10 mg/kg. Following 2 weeks untreated recovery period, differences in fertility and reproductive performance between treatment groups were unremarkable.
In repeat-dose toxicity study conducted in juvenile Beagle dogs at oral doses of 0, 1, 3 and 30 mg/kg/day for 26 weeks duration, the NOAEL was <3 mg/kg (24-fold MRHD) in both sexes. At 30 mg/kg, animals exhibited CNS depression, hypoactivity, decreased respiration rates, lower blood pressure and decrease in reticulocytes, as well as, increases in blood cholesterol and phospholipids. Major histopathology finding corresponded to enlargement of adrenal glands and liver at 30 mg/kg. Toxicology findings were unremarkable after 8 weeks untreated recovery period, except for male pubertal delays noted in the 30 mg/kg group.
Carcinogenesis
The lifetime carcinogenic potential of brexpiprazole was evaluated in two-year studies in mice and rats. In mice, brexpiprazole was administered orally (gavage) at doses of 0.75, 2 and 5 mg/kg/day (1 to 6-fold MRHD on a mg/m2 basis). There was no increase in the incidence of tumors in males at any dose group. In female mice, there was an increased incidence of mammary gland adenocarcinoma and adenosquamous carcinoma, and pars distalis adenoma of the pituitary gland at all doses. In rats, brexpiprazole was administered orally (gavage) at doses of 1, 3 and 10 mg/kg/day in males or 3, 10 and 30 mg/kg/day in females (for males 2 to 24-fold and for females 7 to 73-fold the MRHD). Long-term administration of brexpiprazole to rats did not induce neoplastic lesions.
Proliferative and/or neoplastic changes in the mammary and pituitary glands of rodents have been observed following chronic administration of antipsychotic drugs and are considered to be prolactin mediated. The potential for increasing serum prolactin level of brexpiprazole was shown in both sexes in mice and rats. The relevance for human risk of the findings of prolactin-mediated endocrine tumors in rodents is unknown.
Mutagenesis
Brexpiprazole was not mutagenic when tested in the in vitro bacterial reverse-mutation assay (Ames test), in vivo in the micronucleus assay in rats, and the unscheduled DNA synthesis assay in rats. Brexpiprazole was mutagenic and clastogenic but occurred only at doses that induced cytotoxicity (20-30 µg/mL) in the in vitro forward gene mutation assay in mouse lymphoma cells and in the in vitro chromosomal aberration assay in Chinese hamster ovary cells. Based on a weight of evidence, brexpiprazole is not considered to present a genotoxic risk to humans at therapeutic doses and exposures.
Impairment of Fertility
In female rats treated with brexpiprazole at oral doses of 0, 0.3, 3 or 30 mg/kg/day prior to mating with untreated males and continuing through conception and implantation, the NOAEL in terms of reproductive performance and fertility was 0.3 mg/kg/day (0.7-fold MRHD). Prolonged diestrus and decreased fertility were observed at 3 mg/kg/day. At 30 mg/kg/day a prolongation of the mating phase was observed and significantly increased preimplantation losses were seen.
In male rats treated with brexpiprazole at oral doses of 0, 3, 10 or 100 mg/kg/day for 63 days prior to mating and during copulation (with untreated females), the NOAEL in terms of male fertility and toxicological effects was 10 mg/kg/day (24-fold MRHD).
Reproductive Toxicity
In a prenatal and postnatal developmental study in rats, pregnant dams receiving brexpiprazole at oral doses of 0, 3, 10 and 30 mg/kg/day from implantation until weaning of offspring, the NOAEL for maternal toxicity and newborn viability was 3 mg/kg/day (7-fold MRHD). Increase in the number of stillbirth and death in pups during lactation were observed at 10 and 30 mg/kg. Changes observed at 30 mg/kg/day included impaired nursing in dams, and low birth weight, impaired viability, suppressed body weight gain, delayed pinna unfolding and decreased number of corpora lutea in the offspring.
In a rabbit embryo-fetal development study, pregnant dams receiving brexpiprazole at oral doses of 0, 10, 30 and 150 mg/kg/day during gestation, the NOAEL for reproductive toxicity was 10 mg/kg/day (49-fold MRHD). At doses ≥30 mg/kg, an increase incidence in renal pelvic dilation and caudal vena cava abnormality was observed in fetuses. At 150 mg/kg/day, decreased body weight, retarded ossification, and increased incidences of visceral and skeletal malformations were observed.