


Product Monograph - Jatenzo
1 INDICATIONS
JATENZO (testosterone undecanoate capsules) is indicated for testosterone replacement therapy in adult males for conditions associated with a deficiency or absence of endogenous testosterone (male hypogonadism).
JATENZO should not be used to treat non-specific symptoms suggestive of hypogonadism if testosterone deficiency has not been demonstrated and if other etiologies responsible for the symptoms have not been excluded. Testosterone deficiency should be clearly demonstrated by clinical features and confirmed by two separate validated biochemical assays (morning testosterone) before initiating therapy with any testosterone replacement, including JATENZO treatment.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data in patients under 18 are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
1.2 Geriatrics
Geriatrics (> 65 years of age): There is limited data from clinical trials with JATENZO (testosterone undecanoate capsules) in the geriatric male (>65 years of age) to support the efficacy and safety of prolonged use (see 7.1.4 WARNINGS AND PRECAUTIONS, Geriatrics). Safety and efficacy of JATENZO in men with “age-related hypogonadism” has not been established.
2 CONTRAINDICATIONS
JATENZO (testosterone undecanoate) is contraindicated in:
- Men with carcinoma of the breast or known or suspected carcinoma of the prostate (see 7 WARNINGS AND PRECAUTIONS).
- Women and women who are pregnant. Testosterone can cause virilization of the female fetus when administered to a pregnant woman (see 7.1.1. WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women and see 16 NONCLINICAL TOXICOLOGY).
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Prior to initiating JATENZO, confirm the diagnosis of hypogonadism by ensuring that serum testosterone concentrations have been measured in the morning on at least two separate days and that these testosterone concentrations are below the normal range.
- JATENZO must be taken with food to ensure adequate absorption.
4.2 Recommended Dose and Dosage Adjustment
The recommended starting dose is 237 mg taken orally twice daily, once in the morning and once in the evening. Take JATENZO with food. Capsules should be swallowed without chewing. Individualize the dosage of JATENZO based on the patient's serum testosterone concentration.
To ensure proper dose adjustment, measure serum testosterone concentration 6 hours after the morning dose in plain tubes, clotted at room temperature for 30 minutes prior to centrifugation. Adjust the JATENZO dose based on this serum testosterone measurement as shown in Table 1. Wait seven days after starting treatment or adjusting the dose before checking the serum testosterone concentration. Thereafter, periodically monitor serum testosterone concentrations 6 hours after the morning dose.
Administer the same dose in the morning and evening. The minimum recommended dose is 158 mg twice daily. The maximum recommended dose is 396 mg (two 198 mg capsules) twice daily.
Table 1. JATENZO Dose Adjustment Scheme
| Testosterone Concentration in Serum from Plain Tube Drawn 6 hours After Morning Dose | Current JATENZO Dose (mg, twice daily) | New JATENZO Dose (mg, twice daily) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Less than 425 ng/dL | 158 | 198 | ||||||||
| 198 | 237 | |||||||||
| 237 | 316 (two 158 mg capsules) | |||||||||
| 316 (two 158 mg capsules) | 396 (two 198 mg capsules) | |||||||||
| 425 ng/dL – 970 ng/dL | No Dose Change | |||||||||
| More than 970 ng/dL | 396 (two 198 mg capsules) | 316 (two 158 mg capsules) | ||||||||
| 316 (two 158 mg capsules) | 237 | |||||||||
| 237 | 198 | |||||||||
| 198 | 158 | |||||||||
| 158 | Discontinue Treatment | |||||||||
Among the 155 JATENZO patients who completed the pivotal study, approximately 72% were up-titrated from the initial dose (32% to 316 mg and 40% to 396 mg TU twice daily), 26% remained at their initial oral dose of 237 mg TU twice daily, and 3% were down-titrated (237 to 198 mg TU twice daily).
Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 1 INDICATIONS).
4.5 Missed Dose
If a dose is missed, patients are instructed to skip the dose and take their next scheduled dose. Do not take a double dose of this medicine.
5 OVERDOSE
One case of overdose with JATENZO was reported in clinical trials. This patient inadvertently took a higher dose than prescribed (474 mg twice daily, which is 20% higher than the maximum recommended dose). He did not report any adverse reactions associated with the overdose.
Treatment of overdosage consists of discontinuation of JATENZO and appropriate symptomatic and supportive care. No specific antidote is available.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
JATENZO for oral use is provided as a gelatin capsule containing testosterone undecanoate, a fatty-acid ester of testosterone, dissolved in a proprietary self-emulsifying drug delivery system (SEDDS).
JATENZO capsules are available in three strengths of 158 mg, 198 mg, and 237 mg. All strengths are in oblong shaped capsules. Capsules are packaged as 120 units in wide-mouth, round, white high-density polyethylene (HDPE) bottles with white, polypropylene, child resistant caps and induction-sealed liner.
The 158 mg strength is an opaque red capsule that contains 158 mg of testosterone undecanoate and is imprinted with “158” in white ink. The 198 mg strength is an opaque white capsule that contains 198 mg of testosterone undecanoate and is imprinted with “198” in red ink. The 237 mg strength is an opaque orange capsule that contains 237 mg of testosterone undecanoate and is imprinted with “237” in white ink. The details of the formulation can be found in Table 2.
Gelatin capsule shells are composed of the following inactive ingredients: Ammonium hydroxide, FD&C Yellow #6, gelatin, glycerin, iron oxide red, macrogol, sorbitol, purified water, polyvinyl acetate phthalate, propylene glycol, and titanium dioxide.
Table 2. Dosage Forms, Strengths and Composition
Each capsule may also contain lecithin, medium chain triglycerides, and Phosal 53 MCT, which are processing aids (not non-medicinal ingredients) of the drug products.
7 WARNINGS AND PRECAUTIONS
General
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Capsule – 158 mg, 198 mg, or 237 mg | Borage seed oil, butylated hydroxytoluene, oleic acid, peppermint oil, and polyoxyl 40 hydrogenated castor oil (Cremophor RH 40) |
There is limited data from clinical trials with JATENZO (testosterone undecanoate capsules) in the geriatric male (>65 years of age) to support the efficacy and safety of prolonged use. Impacts to prostate and cardiovascular event rates and patient important outcomes are unknown.
JATENZO is not recommended in men with hypogonadal conditions, such as “age-related hypogonadism”, that are not associated with structural or genetic etiologies. The efficacy of JATENZO has not been established for these conditions.
Testosterone replacement therapy, such as JATENZO, should not be used to attempt to improve body composition, bone and muscle mass, increase lean body mass and decrease total fat mass. Efficacy and safety have not been established. Serious long term deleterious health issues may arise.
Clinical studies have not established testosterone replacement therapy as a treatment for male infertility.
Gynecomastia may develop and persist in patients being treated for hypogonadism.
Carcinogenesis and Mutagenesis
Patients treated with androgens may be at increased risk for prostate cancer. JATENZO is contraindicated in men with known or suspected prostate cancer (see 4 CONTRAINDICATIONS). Patients with clinical or demographic characteristics that are recognized to be associated with an increased risk of prostate cancer should be evaluated for the presence of prostate cancer prior to initiation of testosterone replacement therapy. During the treatment of JATENZO , surveillance for prostate cancer should be consistent with current practices for eugonadal men.
Cardiovascular
Physicians should consider whether the benefits of therapy outweigh the potential cardiovascular risk. Assessment of cardiovascular risk, monitoring and management according to clinical practice and guidelines should be considered.
Increase in Blood Pressure:
JATENZO can increase blood pressure. Ambulatory blood pressure monitoring (ABPM) demonstrated that JATENZO increased systolic /diastolic BP by an average of 4.9/2.5 mmHg from baseline after 4 months of treatment in a phase 3 clinical trial (8 ADVERSE REACTIONS). In patients with hypertension on antihypertensive therapy, JATENZO increased the mean systolic/diastolic BP by 5.4/3.2 mm Hg from baseline. Average blood pressures had not plateaued at the end of the trial.
Before initiating JATENZO, consider the patient’s baseline cardiovascular risk and ensure blood pressure is adequately controlled Monitor blood pressure periodically in men using JATENZO, especially men with hypertension. JATENZO is not recommended for use in patients with uncontrolled hypertension.
Cardiovascular Risk:
The cardiovascular (CV) risk associated with topical testosterone gel was evaluated in the Testosterone Replacement therapy for Assessment of long-term Vascular Events and efficacy ResponSE in hypogonadal men (TRAVERSE) Study. TRAVERSE study was a randomized, double-blind, placebo-controlled, CV outcomes study in men with a history of CV disease or multiple CV risk factors. The results of TRAVERSE showed that topical testosterone gel increased mean systolic blood pressure by
1.8 mmHg from baseline. However, the incidences of major adverse cardiovascular events (MACE), including cardiovascular death, non-fatal myocardial infarction (MI) and non-fatal stroke, were similar between treatment groups (7% for topical testosterone gel vs 7.3% for placebo) (See 8 ADVERSE REACTIONS).
Venous Thromboembolism:
There have been post marketing reports of venous thromboembolic events, including deep vein thrombosis (DVT) and pulmonary embolism (PE), in patients using testosterone replacement products such as JATENZO.
In TRAVERSE Study, a randomized, double-blind, placebo-controlled, cardiovascular (CV) outcomes study, topical testosterone gel was associated with a higher risk of venous thromboembolism (VTE) (1.7% vs 1.2%) which included DVT (0.6% vs 0.5%) and PE (0.9% vs 0.5%) when compared with placebo (See 8 ADVERSE REACTIONS).
Evaluate patients who report symptoms of pain, edema, warmth, and erythema in the lower extremity for DVT and those who present with acute shortness of breath for PE. If a venous thromboembolic event is suspected, discontinue treatment with JATENZO and initiate appropriate workup and management (see 8 ADVERSE REACTIONS).
Edema:
Androgens, including JATENZO, may promote retention of sodium and water. Edema, with or without congestive heart failure, may be a serious complication in patients with pre-existing cardiac, renal, or hepatic disease. In addition to discontinuation of the drug, diuretic therapy may be required.
Dependence, Tolerance and/or Abuse Liability
Controlled Substance
JATENZO contains testosterone undecanoate, which is a Schedule G controlled substance as defined by the Food and Drugs Act.
Abuse
Drug abuse is intentional non-therapeutic use of a drug, even once, for its rewarding psychological and physiological effects. Abuse and misuse of testosterone are seen in male and female adults and adolescents. Testosterone, often in combination with other anabolic androgenic steroids (AAS), and not obtained by prescription through a pharmacy, may be abused by athletes and bodybuilders. There have been reports of misuse by men taking higher doses of legally obtained testosterone than prescribed and continuing testosterone despite adverse events or against medical advice.
Abuse related adverse reactions
- Serious adverse reactions have been reported in individuals who abuse anabolic androgenic steroids. These included cardiac arrest, myocardial infarction, hypertrophic cardiomyopathy, congestive heart failure, cerebrovascular accident, hepatotoxicity, and serious psychiatric manifestations such as major depression, mania, paranoia, psychosis, delusions, hallucinations, hostility and aggression.
- The following adverse reactions have also been reported in men: transient ischemic attacks, convulsions, hypomania, irritability, dyslipidemias, testicular atrophy, subfertility, and infertility.
- The following additional adverse reactions have been reported in women: hirsutism, virilization, deepening of voice, clitoral enlargement, breast atrophy, male-pattern baldness, and menstrual irregularities.
- The following adverse reactions have been reported in male and female adolescents: premature closure of bony epiphyses with termination of growth, and precocious puberty.
Because these reactions are reported voluntarily from a population of uncertain size and may include abuse of other agents, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Dependence
Continued abuse of testosterone and other anabolic steroids, leading to addiction is characterized by the following behaviors:
- Taking greater dosages than prescribed
- Continued drug use despite medical and social problems due to drug use
- Spending significant time to obtain the drug when supplies of the drug are interrupted
- Giving a higher priority to drug use than other obligations
- Having difficulty in discontinuing the drug despite desires and attempts to do so
- Experiencing withdrawal symptoms upon abrupt discontinuation of use
Physical dependence is characterized by withdrawal symptoms after abrupt drug discontinuation or a significant dose reduction of a drug. Individuals taking supratherapeutic doses of testosterone may experience withdrawal symptoms lasting for weeks or months which include depressed mood, major depression, fatigue, craving, restlessness, irritability, anorexia, insomnia, decreased libido and hypogonadotropic hypogonadism.
Drug dependence in individuals using approved doses of testosterone for approved indications has not been documented.
JATENZO has not been studied for its potential to cause dependence, tolerance and/or abuse; however, there may be a theoretical risk of the occurrence of one or more of these risks. Healthcare professionals should consider the patient’s history of drug use and monitor appropriately.
Endocrine and Metabolism
Decreased Thyroxine-binding Globulin:
Androgens, including JATENZO, may decrease concentrations of thyroxin-binding globulin, resulting in decreased total thyroxine (T4) serum concentrations and increased resin uptake of triiodothyronine (T3) and T4. Free thyroid hormone concentrations remain unchanged, however, and there is no clinical evidence of thyroid dysfunction.
Hypercalcemia:
Androgens, including JATENZO, should be used with caution in cancer patients at risk of hypercalcemia (and associated hypercalciuria). Regular monitoring of serum calcium concentrations is recommended during treatment with JATENZO in these patients.
Lipids
Changes in the serum lipid profile may require dose adjustment of lipid lowering drugs or discontinuation of testosterone therapy. Monitor the lipid profile periodically, particularly after starting testosterone therapy.
Genitourinary
Patients with benign prostatic hyperplasia (BPH) treated with androgens are at an increased risk for worsening of signs and symptoms of BPH, and prostate cancer. Monitor patients with BPH for worsening signs and symptoms and evaluate patients for prostate cancer prior to initiating and during treatment with JATENZO (see 2 CONTRAINDICATIONS).
Hematologic
Increases in hematocrit reflective of increases in red blood cell mass, may require lowering the dose or discontinuation of JATENZO. Check that hematocrit is not elevated prior to initiating JATENZO. Evaluate hematocrit approximately every 3 months while the patient is on JATENZO. If hematocrit becomes elevated, stop JATENZO until the hematocrit decreases to an acceptable concentration. If JATENZO is restarted and again causes hematocrit to become elevated, stop JATENZO permanently. An increase in red blood cell mass may increase the risk of thromboembolic events (see 7 WARNINGS AND PRECAUTIONS Cardiovascular).
Hepatic/Biliary/Pancreatic
Prolonged use of high doses of orally active 17-alpha-alkyl androgens (e.g., methyltestosterone) has been associated with serious hepatic adverse effects (peliosis hepatis, hepatic neoplasms, cholestatic hepatitis, and jaundice). Peliosis hepatis can be a life-threatening or fatal complication. Long-term therapy with intramuscular testosterone enanthate has produced multiple hepatic adenomas. JATENZO is not a 17-alpha-alkyl androgens and is not known to produce these adverse effects, because it is metabolized differently. Nonetheless, patients should be instructed to report any signs or symptoms of hepatic dysfunction (e.g. jaundice). If these occur, promptly discontinue JATENZO while the cause is evaluated.
Monitoring and Laboratory Tests
Currently there is no consensus about age specific testosterone levels. The normal serum testosterone level for young eugonadal men is generally accepted to be approximately 10.4-34.6 nmol/L (300-1000 ng/dL). It should be taken into account that physiological testosterone levels (mean and range) decrease with increasing age.
After initiating testosterone therapy, patients should have regular monitoring for the following (see Table 3 below).
Table 3. Testosterone Therapy Monitoring Schedule
| Baseline | 3 Months | 6 Months | Yearly | |
|---|---|---|---|---|
| Symptom evaluation | X | X | X | X |
| Adverse event monitoring | X | X | X | |
| Serum testosterone | X | X | X | X |
| Hematocrit | X | X | X | |
| Prostate-specific antigen (PSA) | X | X | X | X |
| Digital rectal examination (DRE) | X | X |
Psychiatric
Depression and suicidal ideation have been reported in patients treated with JATENZO in clinical trials. Advise patients and caregivers to seek medical attention for manifestations of new onset or worsening depression, suicidal ideation or behavior, anxiety, or other mood changes (see 8 ADVERSE REACTIONS).
Reproductive Health Female and Male Potential
Fertility
With large doses of exogenous androgens, including JATENZO, spermatogenesis may be suppressed through feedback inhibition of pituitary Follicle-stimulating hormone (FSH) possibly leading to adverse effects on semen parameters including sperm count. Patients should be informed of this possible risk when deciding whether to use or to continue to use JATENZO.
Reduced fertility is observed in some men taking testosterone replacement therapy. Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids. With either type of use, the impact on fertility may be irreversible.
Due to lack of controlled studies in women and potential virilizing effects, JATENZO is not indicated for use in women (see 1 INDICATIONS and 7.1.1 Pregnant Women).
Respiratory
The treatment of hypogonadal men with testosterone may potentiate sleep apnea in some patients, especially those with risk factors such as obesity or chronic lung disease.
7.1 Special Populations
7.1.1 Pregnancy
JATENZO is contraindicated in women and pregnant women. Testosterone is teratogenic and may cause fetal harm based on data from animal studies and its mechanism of action (see 2 CONTRAINDICATIONS and 10 CLINICAL PHARMACOLOGY). Exposure of a female fetus to androgens may result in varying degrees of virilization. In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies.
7.1.2 Breastfeeding
JATENZO is not indicated for use in women, and it is unknown how much JATENZO is excreted in human milk.
7.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 1 INDICATIONS).
7.1.4 Geriatrics
There have been a limited number of geriatric patients involved in controlled clinical studies utilizing JATENZO to determine whether efficacy or safety in those over 65 years of age differs from younger subjects. No patients over 65 years of age were enrolled in the pivotal 4-month efficacy and safety clinical study utilizing JATENZO. Additionally, there is insufficient long-term safety data in geriatric patients utilizing JATENZO to assess the potentially increased risk of cardiovascular disease and prostate cancer.
Geriatric patients treated with androgens may also be at risk for worsening of signs and symptoms of BPH (see 7 WARNINGS AND PRECAUTIONS).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Safety of JATENZO was evaluated in Phase 2 and 3 trials, and among the 569 patients that received JATENZO, the following adverse reactions were reported in >2% of the patients: polycythemia, diarrhea, dyspepsia, eructation, peripheral edema, nausea, increased hematocrit, headache, prostatomegaly, and hypertension.
In addition, testosterone has been subject to abuse, typically at doses higher than recommended for the approved indication and in combination with other anabolic androgenic steroids. Anabolic androgenic steroid abuse can lead to serious cardiovascular and psychiatric adverse reactions (see 7 WARNINGS AND PRECAUTIONS, Dependence, Tolerance and/or Abuse Liability).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
The safety of JATENZO was evaluated in a randomized, controlled clinical study with 166 patients treated with JATENZO twice daily with morning and evening meals for approximately 4 months. All patients were started on 237 mg twice daily, then the dose was titrated to 158 mg, 198 mg, 316 mg, or 396 mg twice daily to achieve testosterone concentrations in the eugonadal range. Table 4 summarizes adverse reactions (≥2%) reported in this 4-month study.
Table 4. Number (%) of Patients with Adverse Reactions ≥ 2% in a 4-Month Study with JATENZO
| MedDRA System Organ Class | JATENZO (n = 166) n (%) | |
| MedDRA System Organ Class | JATENZO (n = 166) n (%) | |
| Gastrointestinal Disorders | ||
| Nausea | 4 (2.4) | |
| Investigations | ||
| Hematocrit Increased | 8 (4.8) | |
| High density lipoprotein decreased | 5 (3.0) | |
| Nervous System Disorders | ||
| Headache | 8 (4.8) | |
| Vascular Disorders | ||
| Hypertension | 6 (3.6) | |
Three of the 166 patients (1.8%) in the 4-month study experienced adverse reactions that led to premature discontinuation from the study, including rash (n=1) and headache (n=2).
Among the 569 patients who received JATENZO in all Phase 2 and 3 trials combined, the following adverse reactions were reported in >2% of patients: polycythemia, diarrhea, dyspepsia, eructation, nasopharyngitis, peripheral edema, nausea, increased hematocrit, headache, prostatomegaly, and hypertension. The overall adverse reaction profile of JATENZO from a long-term (12 month) safety study (n=86) was similar to that of the pivotal phase 3 trial.
Blood Pressure Increases
In the 4-month clinical study, 24-hour ABPM was conducted on 180 patients. ABPM was conducted at baseline and at Day 139 of JATENZO therapy. A total of 135 patients in JATENZO group had acceptable ABPM recordings at both time periods and were at least 85% compliant with study drug. In that group, the mean change in 24-hour systolic BP and diastolic BP from baseline to final on-treatment visit on Day 139 (n=135) was 4.9 mmHg (95% CI 3.5, 6.4) and 2.5 mmHg (95% CI 1.5, 3.6), respectively. The mean increase in daytime average, nighttime average, and 24-hour average systolic blood pressure from baseline to Visit 6 for JATENZO group was statistically significantly greater than that of the topical testosterone group; changes in diastolic blood pressure were not significantly different between treatment groups.
The ABPM systolic and diastolic increases were larger in patients with a history of hypertension who were being treated with antihypertensive therapy (5.4 mmHg [95% CI 3.3, 7.6] and 3.2 mmHg [95% CI 1.7, 4.7], respectively [n=67]) compared to patients with no history of hypertension at baseline (4.4 mmHg [95% CI 2.3, 6.4] and 1.8 mmHg [95% CI 0.2, 3.3], respectively [n=63]).
A total of 6 patients were reported to have an adverse reaction of hypertension (2 patients with hypertension and 4 patients with worsening hypertension), and 3 were reported to have an adverse reaction of increased blood pressure. Twelve (7.2%) patients on JATENZO either started antihypertensive medications or had their antihypertensive regimen increased during the study.
Heart Rate Increases
JATENZO increased mean heart rate by an average of 2.2 beats per minute (bpm) [95% CI (1.0, 3.3), N=135] during the study. Patients without a history of hypertension had a greater average increase in mean heart rate (2.7 bpm [95% CI (0.8, 4.6), N=63]) compared to patients with treated hypertension (1.9 bpm [95% CI (0.3, 3.5), N=67)]).
Headaches
Headaches were reported in 8 of the 166 patients (4.8%). Five of these 8 patients had headache events that resolved within 1 to 2 days, three required treatments with analgesics or non-steroidal anti-inflammatory drugs, and 2 led to premature discontinuation from the study.
Cardiovascular Outcomes
TRAVERSE was a randomized, double-blind, cardiovascular outcomes study to assess the cardiovascular (CV) safety of topical testosterone gel compared to placebo in 5,198 hypogonadal men aged 45 to 80 years with a history of CV disease or with multiple CV risk factors. The primary outcome was the incidence of the composite endpoint of major adverse cardiovascular events (MACE), consisting of CV death, non-fatal myocardial infarction (MI), and non-fatal stroke.
The mean duration of therapy was approximately 22 months. The mean duration of follow-up was 33 months. Approximately 61% of all patients discontinued topical testosterone gel or placebo therapy.
The mean patient age (±SD) was 63.3 (7.9) years. Approximately 80% of patients were White, 17% were Black, and 3% were of other races or ethnic groups. Approximately 69%, 84%, and 93% had diabetes mellitus, hyperlipidemia, and hypertension, respectively. Approximately 55% had preexisting cardiovascular disease.
The mean serum testosterone concentration at baseline in patients receiving topical testosterone gel was 220.4 ng/dL (n=2,129). The mean serum testosterone concentrations at 12 months, 24 months, 36 months, and 48 months in patients receiving topical testosterone gel were 440.5 ng/dL (n=1683), 420.9 ng/dl (n=1125), 428.7 ng/dL (n=731), and 365.2 ng/dL (n=220), respectively.
For patients treated with topical testosterone gel, the incidence of MACE was 7.0% (n=182 events) and for those receiving placebo, the incidence of MACE was 7.3% (n=190 events). The study demonstrated non-inferiority of topical testosterone gel versus placebo because the upper bound of 95% CI was less than the pre-specified risk margin, of 1.5 for MACE (Hazard Ratio 0.96 [95% CI: 0.78, 1.17]).
Additional Adverse Reactions Reported in TRAVERSE
Additional adverse reactions reported in TRAVERSE at an incidence rate >2% in either treatment group and greater in topical testosterone gel versus placebo included: nonfatal arrythmias warranting intervention (5.2% vs 3.3%), atrial fibrillation (3.5% vs 2.4%), acute kidney injury (2.3% vs 1.5%) and bone fracture (3.5% vs 2.5%). For the adverse reaction of bone fracture, each event was adjudicated by clinical review.
8.3 Less Common Clinical Trial Adverse Reactions
Following are the adverse events that were reported by <2% of patients during clinical trials of JATENZO.
Depression and suicidal ideation
Two of the 166 patients (1.2%) reported either worsening depression (n=1) or new-onset depression (n=1). One of the 569 patients (0.2%) in clinical trials had suicidal ideation. Each patient completed the study.
Increases in Serum PSA
The mean increase from baseline in PSA was 0.2 ng/mL (n=161). Increases in serum PSA concentrations, defined as an increase from baseline of at least 1.4 ng/mL or PSA greater than 4 ng/mL, occurred in 3 (1.9%) of the patients at the final visit.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
During the 4-month clinical trial of JATENZO, increases in hematocrit were reported in 8 of the 166 (4.8%) patients, which occurred in the second half of the study. Each of the treatment-emergent adverse events of haematocrit increased was considered mild in intensity. None of these increases led to premature discontinuation of JATENZO.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of testosterone. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Cardiovascular Disorders: Myocardial infarction, stroke, venous thromboembolism (see 7 WARNINGS AND PRECAUTIONS).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
- Androgens may decrease blood glucose and therefore may decrease insulin requirements in diabetic patients.
- Changes in anticoagulant activity may be seen with androgens. More frequent monitoring of International Normalized Ratio (INR) and prothrombin time is recommended in patients taking warfarin.
- Use of testosterone with corticosteroids may result in increased fluid retention. Use with caution, particularly in patients with cardiac, renal, or hepatic disease.
- Concomitant administration of medications that are known to increase blood pressure may lead to additional increases in blood pressure when used with JATENZO.
9.3 Drug-Behaviour Interactions
Testosterone has been subject to abuse, typically at doses higher than recommended for the approved indication and in combination with other anabolic androgenic steroids. Anabolic androgenic steroid abuse can lead to serious cardiovascular and psychiatric adverse reactions (see 7 WARNINGS AND PRECAUTIONS).
9.4 Drug-Drug Interactions
The drugs listed below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Insulin:
Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may necessitate a decrease in the dose of anti-diabetic medication.
Oral Vitamin K Antagonist Anticoagulants:
Changes in anticoagulant activity may be seen with androgens; therefore, more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking warfarin, especially at the initiation and termination of androgen therapy.
Corticosteroids:
The concurrent use of testosterone with corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal, or hepatic disease.
Medications that May Also Increase Blood Pressure:
Some prescription medications and nonprescription analgesic and cold medications contain ingredients known to increase blood pressure. Concomitant administration of these medications with JATENZO may lead to additional increases in blood pressure (see 7 WARNINGS AND PRECAUTIONS – Cardiovascular).
Effect of JATENZO on Other Drugs
A Drug-Drug Pharmacokinetic Interaction study was carried out between JATENZO® (Testosterone Undecanoate) and Cytochrome P450 3A4 Substrate (Midazolam), P-glycoprotein Substrate (Digoxin), and Breast Cancer Resistance Protein Substrate (Rosuvastatin) in healthy adult male subjects (TOL-CLAR-22030, a Phase I, Open-label, Two-Period, Fixed-Sequence Study). The results of this study suggest that the administration of JATENZO did not cause statistically significant increases in the systemic exposure of CYP3A4, P-gp and BCRP substrates (see Error! Reference source not found. Error! Reference source not found.). The potential for JATENZO doses >237 mg to inhibit CYP3A4, P-gp and BCRP is unknown.
9.5 Drug-Food Interactions
JATENZO should be taken with food as fat enhances absorption of JATENZO (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Androgens, including JATENZO, may decrease concentrations of thyroxin-binding globulin, resulting in decreased total T4 serum concentrations and increased resin uptake of T3 and T4. Free thyroid hormone concentrations remain unchanged, however, and there is no clinical evidence of thyroid dysfunction.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Testosterone undecanoate, an orally active testosterone preparation, is a fatty acid ester of the natural androgen testosterone. Unlike other oral testosterone preparations, testosterone undecanoate is able to by-pass the liver via the lymphatic system and is therefore orally bioavailable.
Therapy with testosterone undecanoate increases plasma levels of testosterone and its active metabolites, leading to a regular therapeutic effect.
Testosterone undecanoate delivers physiologic amounts of testosterone, producing circulating testosterone levels that approximate normal levels (10.4-34.6 nmol/L, or 300-1000 ng/dL) seen in young healthy men.
10.2 Pharmacodynamics
Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis, and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement, vocal cord thickening, alterations in body musculature and fat distribution.
Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter syndrome or Leydig cell aplasia, whereas secondary hypogonadism (also known as hypogonadotropic hypogonadism) is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
10.3 Pharmacokinetics
Absorption
JATENZO delivers physiologic amounts of testosterone, producing testosterone concentrations that approximate normal concentrations seen in healthy men.
The JATENZO self-emulsifying drug delivery system is well absorbed from the gastrointestinal tract. Testosterone undecanoate is absorbed via the lymphatic system, circumventing first passage through the liver.
Following oral administration an important part of the active substance testosterone undecanoate is co-absorbed with the lipophilic solvent from the intestine into the lymphatic system, thus partially circumventing the first-pass inactivation by the liver. JATENZO must be taken with a normal meal or breakfast to ensure absorption.
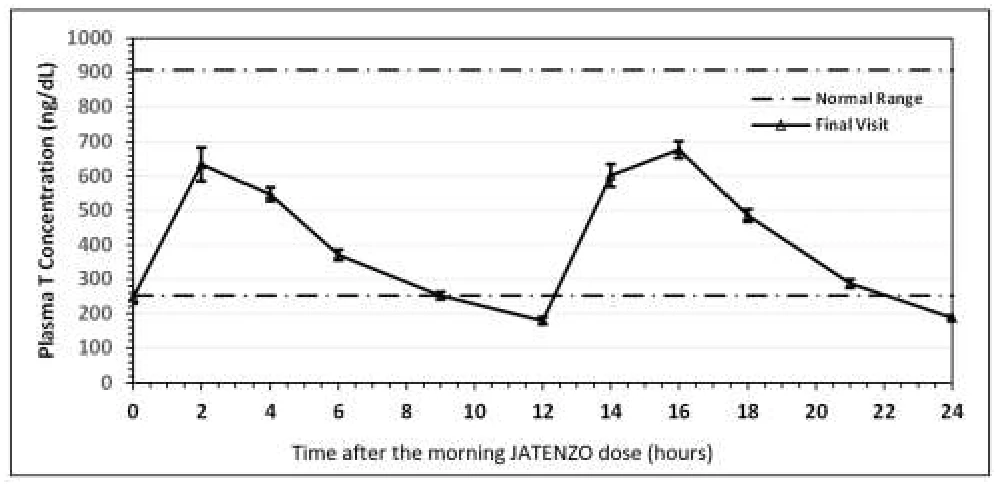
JATENZO was taken orally at a starting dose of 237 mg twice per day with meals in a multicenter, open-label, randomized, 2-arm, active-controlled trial in hypogonadal males. The dose was adjusted, as needed, on Days 14 and 56 between a minimum of 158 mg twice per day and a maximum of 396 mg twice per day based on the average plasma testosterone concentration obtained over 24 hours after the morning dose. The average daily NaF-EDTA plasma testosterone concentration was 403 (± 128) ng/dL at the end of treatment, where the normal eugonadal range in NaF-EDTA plasma was 252-907 ng/dL in this study. Note that the titration scheme for use in clinical practice is based on serum total testosterone (see 4 DOSAGE AND ADMINISTRATION).
Table 5 summarizes the pharmacokinetic (PK) parameters for plasma total testosterone in patients completing at least 105 days of JATENZO treatment administered twice daily.
Table 5. NaF-EDTA Plasma Testosterone Cavg and Cmax at Final PK Visit
| PK Parameter | All Doses (N = 151) | ||||
| Cavg (ng/dL) | Mean | 403 | |||
| SD | 128 | ||||
| Cmax (ng/dL) | Mean | 1008 | |||
| SD | 581 | ||||
PK = pharmacokinetic; Cavg = 24-hour average concentration; Cmax = maximum concentration
Figure 1 summarizes the mean plasma total testosterone profile for the patients at the final PK visit.
Figure 1. Mean (±SEM) Concentration-Time Profile for NaF-EDTA Plasma Total Testosterone in JATENZO Treated Subjects at Final PK Visit
SEM = standard error of the mean; T = testosterone
When JATENZO was dosed with different breakfasts containing various amounts of fat, the bioavailability with the 30 g fat, 45 g fat, and high-calorie high-fat breakfasts was comparable, but there was a food effect with the 15 g fat breakfast compared to the 30 g fat breakfast. The 15 g fat breakfast had a 25% decrease in testosterone exposure compared to the 30 g fat breakfast.
Distribution
Circulating testosterone is primarily bound in serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins.
Metabolism
The androgenic activity of testosterone undecanoate occurs after the ester bond linking the testosterone to the undecanoic acid is cleaved by endogenous non-specific esterases. Undecanoic acid is metabolized like all fatty acids via the beta-oxidation pathway.
Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are dihydrotestosterone (DHT) and estradiol.
Elimination
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
Drug Interaction Studies
Clinical Pharmacology Studies
Concomitant administration of JATENZO at 237 mg dose with midazolam (CYP3A4 substrate), digoxin (P-gp substrate), and rosuvastatin (BCRP substrate) had no clinically meaningful effect on the concentration of these substrates.
The potential for JATENZO doses >237 mg to inhibit CYP3A4, P-gp and BCRP is unknown.
Special Populations and Conditions
- Pediatrics: Safety and efficacy of JATENZO in males less than 18 years old have not been established (see 7.1 Special Populations).
- Geriatrics: There are limited long term safety data to assess the potential risks of cardiovascular disease and prostate cancer (see 7 WARNINGS AND PRECAUTIONS).
- Sex: Only male patients were included in JATENZO clinical trials. JATENZO is not indication for use in women (see 1 INDICATIONS).
- Genetic Polymorphism: The effect of genetic polymorphism on the pharmacokinetics of JATENZO has not been studied.
- Ethnic Origin: The effect of race and ethnicity were not clinically significant factors in the observed pharmacokinetics of JATENZO.
- Hepatic Insufficiency: No studies were conducted in patients with hepatic insufficiency.
- Renal Insufficiency: No studies were conducted in patients with renal insufficiency.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (20°C to 25°C). Protect from moisture. Avoid refrigerated storage (2°C to 8°C).
Keep JATENZO out of reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Non-proprietary name of the drug product(s): Testosterone Undecanoate
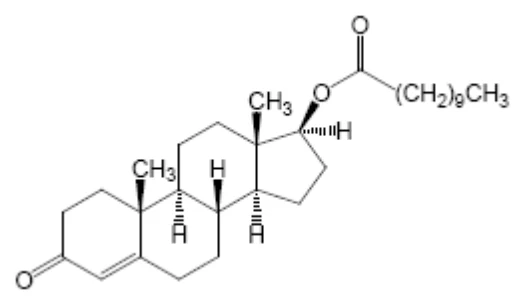
Chemical name: 17β-hydroxyandrost-4-en-3-one undecanoate
Molecular formula: C30H48O3,
Molecular mass: 456.7 g/mol
Structural formula:
Physicochemical properties: Testosterone undecanoate is a creamy white crystalline powder, that is insoluble in water. Melting point of testosterone undecanoate is 63°C.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
14.1.1 Testosterone Replacement in Adult Males
The pivotal phase 3 trial enrolled men between 18 and 65 years of age with a clinical diagnosis of hypogonadism. This trial excluded subjects who had significant diseases such as liver, kidney, uncontrolled or poorly controlled heart disease, including hypertension, congestive heart failure or coronary heart disease, or psychiatric illness, including severe depression. Subjects with a recent (within 2 years) history of stroke, transient ischemic attack, or acute coronary event, uncontrolled hypertension, angina or stent (coronary or carotid) placement were also excluded. Subjects with a body mass index ≥ 38 kg/m2 were excluded.
A total of 166 men were treated with JATENZO. The age of study subjects ranged from 24 to 65 years, with a mean of 51.6 years. Approximately 80.1% subjects were White and 17.5% were African American. The mean body mass index (BMI) was 31.8 kg/m2 with the majority of the subjects categorized as overweight (30.0%) or obese (65.1%).
JATENZO was taken orally at a starting dose of 237 mg twice per day with meals. The dose was adjusted on Days 21 and 56 between a minimum of 158 mg twice per day and a maximum of 396 mg twice per day on the basis of the average testosterone concentration obtained over 24 hours post-morning dose.
The primary endpoint was the percentage of patients with mean plasma total testosterone concentration (Cavg) over 24-hours within the normal eugonadal range on the final PK visit of the study. Secondary endpoints were the percentage of patients with a maximum total testosterone concentration (Cmax) above three predetermined limits: less than or equal to 1500 ng/dL, between 1800 and 2500 ng/dL, and greater than 2500 ng/dL.
One hundred and forty-five (87.3%, with a 95%CI of 81.3%,92.0) of the 166 hypogonadal men who received JATENZO had a mean total testosterone concentration (Cavg) within the normal eugonadal range at the end of treatment.
The percentage of patients who received JATENZO and had Cmax less than or equal to 1500 ng/dL, between 1800 and 2500 ng/dL, and greater than 2500 ng/dL at the final PK visit were 90.7% , 2%, and 2%, respectively. The titration scheme for use in clinical practice is based on serum total testosterone (see 4 DOSAGE AND ADMINISTRATION).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: JATENZO has been evaluated in 3- and 9-month repeat-dose oral toxicity studies in male eugonadal dogs. JATENZO caused exaggerated pharmacological effects on androgen-responsive tissues including testes, epididymis, prostate, and adrenals at exposures to testosterone or testosterone undecanoate, comparable to the maximum human exposure based on AUC comparisons. Following a 4-week drug-free period, a reduced severity of these findings was observed, suggesting partial reversibility.
In adrenal glands, moderate to severe atrophy, characterized as thinning of the zona fasciculata, was observed with reduced adrenal weights, and reduced circulating levels of cortisol in testosterone undecanoate-treated dogs after 3 months of treatment. Following 9-month treatment, there were dose-related decreases in adrenal weights in testosterone undecanoate-treated male dogs and moderate adrenal vacuolation in one testosterone undecanoate-treated male dog. The clinical significance of these adrenal and cortisol findings is unknown.
Genotoxicity: Testosterone undecanoate was negative in the in vitro Ames and in the in vivo rat micronucleus assays.
Carcinogenicity: Testosterone propionate (a testosterone ester prodrug pharmacologically similar to TU) has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors, which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma. In male rats, subcutaneous implantation of testosterone propionate has produced prostatic adenocarcinomas. In a 26-week oral carcinogenicity of Testosterone Undecanoate performed in male CByB6F1-Tg(HRAS)2Jic (tg/wt) Mice, no increase in neoplastic or non-neoplastic lesions was shown in the TU treated mice compared to the controls. Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats.
Reproductive and Developmental Toxicology: The administration of exogenous testosterone suppresses spermatogenesis in the rat, dog, and non-human primates, which was reversible on cessation of the treatment.