


Product Monograph - Jubbonti
RECENT MAJOR LABEL CHANGES
| Not applicable |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed .
RECENT MAJOR LABEL CHANGES............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics .......................................................................................................... 5
1.2 Geriatrics........................................................................................................... 5
2 CONTRAINDICATIONS ................................................................................................. 5
4 DOSAGE AND ADMINISTRATION................................................................................. 6
4.1 Dosing Considerations ....................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment..................................................... 6
4.4 Administration................................................................................................... 6
4.5 Missed Dose ...................................................................................................... 7
5 OVERDOSAGE ............................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 7
7 WARNINGS AND PRECAUTIONS .................................................................................. 8
7.1 Special Populations .......................................................................................... 12
7.1.1 Pregnant Women ....................................................................................... 12
7.1.2 Breast-feeding............................................................................................ 12
7.1.3 Pediatrics ................................................................................................... 13
7.1.4 Geriatrics ................................................................................................... 13
8 ADVERSE REACTIONS ................................................................................................ 15
8.1 Adverse Reaction Overview.............................................................................. 15
8.2 Clinical Trial Adverse Reactions ........................................................................ 15
8.3 Less Common Clinical Trial Adverse Reactions .................................................. 43
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data ...................................................................................................... 47
8.5 Postmarket Adverse Reactions ......................................................................... 47
9 DRUG INTERACTIONS................................................................................................ 48
9.2 Drug interactions Overview.............................................................................. 48
9.3 Drug-Behavioural Interactions.......................................................................... 48
9.4 Drug-Drug Interactions .................................................................................... 48
9.5 Drug-Food Interactions .................................................................................... 48
9.6 Drug-Herb Interactions .................................................................................... 48
9.7 Drug-Laboratory Test Interactions .................................................................... 48
10 CLINICAL PHARMACOLOGY ....................................................................................... 49
10.1 Mechanism of Action.................................................................................. 49
10.2 Pharmacodynamics .................................................................................... 50
10.3 Pharmacokinetics ....................................................................................... 50
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 52
12 SPECIAL HANDLING INSTRUCTIONS........................................................................... 53
PART II: SCIENTIFIC INFORMATION ...................................................................................... 54
13 PHARMACEUTICAL INFORMATION............................................................................ 54
14 CLINICAL TRIALS........................................................................................................ 54
14.5 Clinical Trials - Reference Biologic Drug ....................................................... 54
15 MICROBIOLOGY ........................................................................................................ 64
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 64
17 SUPPORTING PRODUCT MONOGRAPHS.................................................................... 70
PATIENT MEDICATION INFORMATION ................................................................................. 71
JUBBONTI® (denosumab) is a biosimilar biologic drug (biosimilar) to PROLIA®. A biosimilar is a biologic drug that was granted authorization based on a demonstration of similarity to a version previously authorized in Canada, known as the reference biologic drug.
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Indications have been granted on the basis of similarity between JUBBONTI and the reference biologic drug PROLIA®.
JUBBONTI (denosumab injection) is indicated:
Postmenopausal Osteoporosis
for the treatment of postmenopausal women with osteoporosis at high risk for fracture, defined as a history of osteoporotic fracture, or multiple risk factors for fracture; or patients who have failed or are intolerant to other available osteoporosis therapy. In postmenopausal women with osteoporosis, JUBBONTI reduces the incidence of vertebral, nonvertebral and hip fractures (see 14 CLINICAL TRIALS).
Treatment to Increase Bone Mass in Men with Osteoporosis at High Risk for Fracture
as a treatment to increase bone mass in men with osteoporosis at high risk for fracture, defined as a history of osteoporotic fracture, or multiple risk factors for fracture; or patients who have failed or are intolerant to other available osteoporosis therapy (see 14 CLINICAL TRIALS).
Treatment to Increase Bone Mass in Men with Nonmetastatic Prostate Cancer receiving Androgen Deprivation Therapy (ADT), who are at high risk for fracture
as a treatment to increase bone mass in men with nonmetastatic prostate cancer receiving androgen deprivation therapy (ADT), who are at high risk for fracture (see 14 CLINICAL TRIALS).
Treatment to Increase Bone Mass in Women Receiving Adjuvant Aromatase Inhibitor Therapy for Nonmetastatic Breast Cancer
as a treatment to increase bone mass in women with nonmetastatic breast cancer receiving adjuvant aromatase inhibitor (AI) therapy, who have low bone mass and are at high risk for fracture (see 14 CLINICAL TRIALS).
Treatment to Increase Bone Mass for the Treatment and Prevention of Glucocorticoid-Induced Osteoporosis in Women and Men at High Risk for Fracture
- as a treatment to increase bone mass in women and men at high risk for fracture due to sustained systemic glucocorticoid therapy (see 14 CLINICAL TRIALS).
- as a treatment to increase bone mass in women and men at high risk for fracture who are starting or have recently started long term glucocorticoid therapy (see 14 CLINICAL TRIALS).
1.1 Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of denosumab in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
1.2 Geriatrics
Geriatrics (≥ 65 years of age): The majority of patients treated with denosumab in the postmenopausal osteoporosis (PMO) clinical trial were ≥ 65 years old (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
- Of the patients in the osteoporosis study in men, 133 patients (55%) were ≥ 65 years old, while 39 patients (16%) were ≥ 75 years old.
- In the clinical trial of men with bone loss associated with ADT for nonmetastatic prostate cancer, 1364 patients (93%) were ≥ 65 years old.
- In a clinical trial of women with bone loss associated with adjuvant AI therapy for breast cancer, 76 patients (30%) were ≥ 65 years old.
- In a clinical trial of patients with glucocorticoid-induced osteoporosis, 355 patients (44.7%) were ≥ 65 years old.
2 CONTRAINDICATIONS
- Jubbonti is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING. Anaphylactic reactions have been reported (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity and 8 ADVERSE REACTIONS, Postmarket Adverse Drug Reactions).
- Hypocalcemia (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
- Female patients who are pregnant or who are trying to become pregnant. Jubbonti may cause fetal harm when administered to a pregnant woman. In women of reproductive potential, pregnancy testing should be performed prior to initiating treatment with Jubbonti. In utero denosumab exposure in cynomolgus monkeys resulted in increased fetal loss, stillbirths, and postnatal mortality, along with evidence of absent lymph nodes, abnormal bone growth and decreased neonatal growth. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to a fetus (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Jubbonti is intended for use under the guidance and supervision of physicians who have fully familiarized themselves with the efficacy/safety profile of Jubbonti. After an initial training in proper subcutaneous injection technique, patients may self -inject Jubbonti if a physician determines that is appropriate and with medical follow-up as necessary. Patients should be informed that serious hypersensitivity reactions including anaphylaxis have been reported with denosumab injections.
Pregnancy must be ruled out prior to administration of Jubbonti. Perform pregnancy testing in all women of reproductive potential prior to administration of Jubbonti. Based on findings in animals, denosumab may cause fetal harm when administered to pregnant women (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS and 16 NON-CLINICAL TOXICOLOGY, Animal Toxicology).
Patients must be adequately supplemented with calcium and vitamin D at the recommended dosesa.
4.2 Recommended Dose and Dosage Adjustment
Health Canada has not authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
The recommended dose of Jubbonti (denosumab) is a single SC injection of 60 mg, once every 6 months.
4.4 Administration
Administration of Jubbonti should be performed by an individual who has been adequately trained in injection techniques.
The prefilled syringe with safety guard is not made with natural rubber latex.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit. Jubbonti is a clear, colourless to slightly yellowish or slightly brownish solution. Do not use if the solution is cloudy or if the solution contains visible particles or foreign particulate matter.
Prior to administration, Jubbonti may be allowed to reach room temperature (up to 25oC) in the original carton. This generally takes 15 to 30 minutes.
Administer Jubbonti via SC injection in the upper arm, the upper thigh, or the abdomen.
a2010 clinical practice guidelines for the diagnosis and management of osteoporosis in Canada: summary
4.5 Missed Dose
If a dose is missed, it should be given as soon as convenient. The next dose should be scheduled 6 months from the date of the previous injection.
5 OVERDOSAGE
There is no experience with overdosage with denosumab.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 Dosage Forms, Strengths, Composition and Packaging
Jubbonti is a sterile, preservative-free, clear, colourless to slightly yellowish or slightly brownish solution formulated at pH 5.2.
Jubbonti is supplied in a single use prefilled syringe with a 29 gauge ½ inch needle with a BD UltraSafe PlusTM** Passive Safety Guard. The prefilled syringe with safety guard is not made with natural rubber latex.
Each 1.0 mL single use prefilled syringe of Jubbonti contains 60 mg denosumab, 17 mM acetic acid, 0.1 mg polysorbate 20, 0.499 mg sodium hydroxide , 47 mg sorbitol, water for injection, hydrochloric acid, and sodium hydroxide to a pH of 5.2.
Jubbonti is supplied in a dispensing pack containing one prefilled syringe.
Description
Jubbonti is a genetically engineered human IgG2 kappa type monoclonal antibody that targets the transmembrane or soluble receptor activator of nuclear factor kappa-B ligand (RANKL). The antibody is produced using recombinant DNA technology in a Chinese Hamster Ovary mammalian cell expression system.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Subcutaneous | Solution for injection / 60 mg denosumab in 1 mL solution in a single use prefilled syringe (PFS) | Acetic acid, hydrochloric acid, polysorbate 20, sodium hydroxide, sorbitol, water for injection |
7 WARNINGS AND PRECAUTIONS
General
Adequate intake of calcium and vitamin D is important in all patients.
Patients being treated with Jubbonti should not be treated concomitantly with other denosumab-containing medicinal products.
Atypical Femoral Fractures
Atypical femoral fractures have been reported in patients receiving denosumab. Atypical femoral fractures may occur with little or no trauma in the subtrochanteric and diaphyseal regions of the femur and may be bilateral. Specific radiographic findings characterize these events. Atypical femoral fractures have also been reported in patients with certain comorbid conditions (eg, vitamin D deficiency, rheumatoid arthritis, hypophosphatasia) and with use of certain pharmaceutical agents (eg, bisphosphonates, glucocorticoids, proton pump inhibitors). These events have also occurred without antiresorptive therapy. During Jubbonti treatment, patients should be advised to report new or unusual thigh, hip, or groin pain. Patients presenting with such symptoms should be evaluated for an incomplete femoral fracture, and the contralateral femur should also be examined.
Endocrine and Metabolism
Hypercalcemia in Pediatric Patients with Osteogenesis Imperfecta
Jubbonti is not indicated for use in pediatric patients.
In clinical trials, hypercalcemia has been reported in pediatric patients with osteogenesis imperfecta treated with denosumab. Some cases required hospitalization (see Special Populations, Pediatrics).
Hypocalcemia
Hypocalcemia must be corrected by adequate intake of calcium and vitamin D prior to initiating therapy with Jubbonti. Other disorders affecting mineral metabolism (such as vitamin D deficiency) should be treated.
Clinical monitoring of calcium levels is recommended before each dose and, in patients predisposed to hypocalcemia within two weeks after the initial dose (see Monitoring and Laboratory Tests).
Patients are advised to report to their physicians any symptoms of hypocalcemia, such as paresthesias or muscle spasms, twitching and muscle cramps (8 ADVERSE REACTIONS, Hypocalcemia). Calcium levels should be measured if any patient presents with suspected symptoms of hypocalcemia during treatment.
In the postmarket setting, severe symptomatic hypocalcemia (resulting in hospitalization, life-threatening events, and fatal cases) has been reported, particularly in patients with severe renal impairment, receiving dialysis or treatment with other calcium lowering drugs (see 8 ADVERSE REACTIONS, Postmarket Adverse Drug Reactions, Severe Hypocalcemia). While most cases occured in the first weeks of initiating therapy, it can also occur later. Examples of the clinical manifestations of severe symptomatic hypocalcemia have included QT interval prolongation, tetany, convulsions and altered mental status.
Hepatic Impairment
The safety and efficacy of denosumab have not been studied in patients with hepatic impairment.
Hypersensitivity
Clinically significant hypersensitivity reactions including anaphylaxis have been reported with denosumab. Symptoms have included hypotension, dyspnea, throat tightness, facial and upper airway edema, pruritus, and urticaria.
If an anaphylactic or other clinically significant allergic reaction occurs, initiate appropriate treatment immediately and discontinue further use of Jubbonti (see 2 CONTRAINDICATIONS and 8 ADVERSE REACTIONS).
Infections
In a 3-year clinical trial in women with postmenopausal osteoporosis, serious infections leading to hospitalization were reported more frequently in the denosumab group (4.1%) than in the placebo group (3.4%). Skin infections leading to hospitalization were reported more frequently in the denosumab (0.4%) versus the placebo (< 0.1%) groups. These cases were predominantly cellulitis. As well, infections of the abdomen, urinary tract, and ear, were more frequent in patients treated with denosumab. Endocarditis was also reported more frequently in denosumab-treated patients (< 0.1% denosumab group; 0% placebo group). The incidence of opportunistic infections was balanced between denosumab and placebo groups and the overall incidence of skin infections was similar between the denosumab (1.5%) and placebo (1.2%) groups. Patients should be advised to seek prompt medical attention if they develop signs or symptoms of severe infection, including cellulitis and erysipelas (see 8 ADVERSE REACTIONS, Infections).
Patients on concomitant immunosuppressant agents (eg, glucocorticoids) or with impaired immune systems may be at increased risk for serious infections. Limited information is available on the safety of denosumab treatment in patients with glucocorticoid-induced osteoporosis who have a clinically important active infection, or a history of recurrent or chronic infections. Consider the benefit-risk profile in such patients before treating with Jubbonti. In patients who develop serious infections while on Jubbonti, prescribers should assess the need for continued Jubbonti therapy.
Malignancies
See 8 ADVERSE REACTIONS, Clinical Trial Adverse Reactions.
Monitoring and Laboratory Tests
Clinical monitoring of calcium is recommended before each dose. In patients with a history of hypocalcemia, or signs and symptoms of hypocalcemia or predisposed to hypocalcemia (eg, history of hypoparathyroidism, thyroid surgery, parathyroid surgery, malabsorption syndromes, excision of small intestine, severe renal impairment [creatinine clearance < 30 mL/min] or receiving dialysis or treatment with other calcium lowering drugs), clinical monitoring of calcium levels is recommended within the first 2 weeks of the initial dose. Calcium levels should be measured if any patient presents with suspected symptoms of hypocalcemia during treatment (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
Multiple Vertebral Fractures (MVF) Following Treatment Discontinuation
Multiple vertebral fractures (MVF) may occur following discontinuation of treatment with Jubbonti, particularly in patients with a history of vertebral fracture.
Advise patients not to interrupt Jubbonti therapy without their physician’s advice. Evaluate the individual benefit-risk before discontinuing treatment with Jubbonti. If Jubbonti treatment is discontinued, consider transitioning to an alternative antiresorptive therapy.
Osteonecrosis of the Jaw (ONJ)
Osteonecrosis of the jaw (ONJ) has been reported in patients treated with denosumab or bisphosphonates, another class of anti-resorptive agents. Most cases have been in cancer patients; however, some have occurred in patients with osteoporosis. The risk of ONJ may increase with duration of exposure to denosumab. ONJ has been reported in clinical studies in patients receiving denosumab at a dose of 60 mg every 6 months for osteoporosis. There have been reports of ONJ in clinical studies in patients with advanced cancer treated with denosumab at the studied dose of 120 mg administered every 4 weeks.
Known risk factors for ONJ include previous treatment with bisphosphonates, older age, smoking, a diagnosis of cancer, concomitant therapies (eg, chemotherapy, antiangiogenic biologics, corticosteroids, radiotherapy to head and neck), poor oral hygiene, invasive dental procedures (eg, dental extractions, dental implants, oral surgery), and co-morbid disorders (eg, periodontal and/or other pre-existing dental disease, ill-fitting dentures, anemia, coagulopathy, infection).
It is important to evaluate patients for risk factors for ONJ before starting treatment. A dental examination with appropriate preventative dentistry is recommended prior to treatment with Jubbonti in patients with risk factors for ONJ.
Good oral hygiene practices should be maintained during treatment with Jubbonti. Patients should receive routine dental check-ups, and immediately report any oral symptoms such as dental mobility, pain or swelling during treatment with Jubbonti.
Avoid invasive dental procedures during treatment with Jubbonti. For patients in whom invasive dental procedures cannot be avoided, the clinical judgment of the treating physician should guide the management plan of each patient based on individual benefit -risk assessment.
Patients who are suspected of having ONJ or patients who develop ONJ during treatment with Jubbonti should receive care by a dentist or an oral surgeon. In patients who develop ONJ during treatment with Jubbonti, a temporary interruption of treatment should be considered based on individual benefit-risk assessment until the condition resolves (see 8 ADVERSE REACTIONS, Osteonecrosis of the Jaw (ONJ)).
Renal Impairment
In a study of 55 patients with varying degrees of renal function, including patients on dialysis, the degree of renal impairment had no effect on the pharmacokinetics of denosumab; thus, dose adjustment for renal impairment is not necessary.
In clinical studies, patients with severe renal impairment (creatinine clearance < 30 mL/min) or receiving dialysis were at greater risk of developing hypocalcemia. Adequate intake of calcium and vitamin D is important in patients with severe renal impairment or receiving dialysis (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
Skin
In a large, 3-year clinical trial of over 7800 women with postmenopausal osteoporosis, epidermal and dermal adverse events such as dermatitis, eczema, and rashes occurred at a significantly higher rate in the denosumab (10.8%) group compared to the placebo (8.2%) group. Most of these events were not specific to the injection site. Consider discontinuing Jubbonti if severe symptoms develop (see 8 ADVERSE REACTIONS, Skin).
Suppression of Bone Turnover
In clinical trials in women with postmenopausal osteoporosis, treatment with denosumab resulted in significant suppression of bone remodeling as evidenced by markers of bone turnover and bone histomorphometry. The significance of these findings and the effect of long-term treatment with denosumab are unknown. Monitor patients for osteonecrosis of the jaw, atypical fractures, and delayed fracture healing (see 8 ADVERSE REACTIONS, Fracture Healing, Osteonecrosis of the Jaw (ONJ); 10 CLINICAL PHARMACOLOGY, Pharmacodynamics; 13 Product Characteristics: Denosumab is produced in genetically engineered mammalian (Chinese Hamster Ovary) cells. CLINICAL TRIALS, Bone Histology and Histomorphometry).
7.1 Special Populations
7.1.1 Pregnant Women
There have been no studies of denosumab in pregnant women.
Jubbonti is contraindicated in pregnant women and in women trying to conceive. Verify the pregnancy status of women of reproductive potential prior to initiating Jubbonti treatment. Advise women of reproductive potential of the risk of Jubbonti use in pregnancy and to use effective contraception during therapy; and for at least 5 months after the last dose of Jubbonti.
Denosumab may cause fetal harm when administered to a pregnant woman based on findings in animal studies (see 2 CONTRAINDICATIONS, 4 DOSAGE AND ADMINISTRATION and 16 NON-CLINICAL TOXICOLOGY, Animal Toxicology).
Developmental toxicity studies have been performed in cynomolgus monkeys at AUC exposures of up to 100-fold higher than the human exposure. No evidence of impaired fertility was observed.
In a study of cynomolgus monkeys dosed with denosumab during the period equivalent to the first trimester at AUC exposures up to 99-fold higher than the human dose (60 mg every 6 months), there was no evidence of maternal or fetal harm. In this study, fetal lymph nodes were not examined.
In another study, in utero denosumab exposure in cynomolgus monkeys at 50 mg/kg body weight every 4 weeks, from gestation day 20 through to parturition resulted in increased fetal loss, stillbirths and post-natal mortality. Findings in the infants included skeletal abnormalities resulting from impaired bone resorption during rapid growth, reduced bone strength and treatment-related bone fractures; reduced hematopoiesis; tooth malalignment and dental dysplasia (in the absence of adverse effects on tooth eruption); absence of peripheral lymph nodes; and decreased neonatal growth. There was no evidence of maternal toxicity. Maternal mammary gland development was normal.
Studies in mice suggest absence of RANKL during pregnancy may interfere with maturation of the mammary gland leading to impaired lactation postpartum (see 16 NON-CLINICAL TOXICOLOGY, Animal Toxicology).
7.1.2 Breast-feeding
Jubbonti is not recommended for use in nursing women (see also Pediatrics below). It is not known whether denosumab is excreted into human milk. Because Jubbonti has the potential to cause adverse reactions in nursing infants, a decision should be made whether to discontinue nursing or discontinue the drug.
Males
In healthy men administered a single dose of denosumab, denosumab was present in the seminal fluid at maximum concentrations corresponding to approximately 0 to 5% of that present in serum. It is unlikely that a female partner or embryo/fetus would be exposed to pharmacologically relevant concentrations of denosumab via seminal fluid following unprotected sexual intercourse with a male partner treated with Jubbonti (10 CLINICAL PHARMACOLOGY, Pharmacokinetics).
7.1.3 Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Jubbonti in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
In clinical trials, hypercalcemia has been reported very commonly in pediatric patients with osteogenesis imperfecta treated with denosumab. Some cases required hospitalization and were complicated by acute renal injury (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Adolescent primates (cynomolgus monkeys) dosed with denosumab at 27 and 150 times (10 and 50 mg/kg dose) the clinical exposure based on AUC had abnormal growth plates. In neonatal rats, inhibition of RANKL (target of denosumab therapy) with a construct of osteoprotegerin bound to Fc (OPG-Fc) at high doses was associated with inhibition of bone growth and tooth eruption. Therefore, treatment with denosumab may inhibit bone growth in children with open growth plates and may inhibit eruption of dentition. In neonatal cynomolgus monkeys exposed in utero to denosumab at 50 mg/kg, there was increased post-natal mortality; skeletal abnormalities resulting from impaired bone resorption during rapid growth, reduced bone strength and treatment-related bone fractures; reduced hematopoiesis; tooth malalignment and dental dysplasia (in the absence of adverse effects on tooth eruption); absence of peripheral lymph nodes; and decreased neonatal growth. Following a recovery period from birth out to 6 months of age, findings still observed were mildly reduced bone length (femoral, vertebral, jaw), reduced cortical thickness with associated reduced strength; extramedullary hematopoiesis; dental dysplasia; and the absence or decreased size of some lymph nodes. One infant had minimal to moderate mineralization in multiple tissues (see 16 NON-CLINICAL TOXICOLOGY, Animal Toxicology).
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age)
Females
In the PMO clinical trial, 94.7% of the patients who received denosumab were ≥ 65 years old and 31.6% were ≥ 75 years old. No overall differences in safety or efficacy were observed between patients ≥ 65 years old and patients ≥ 75 years old. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
In a clinical trial of women with bone loss associated with adjuvant AI therapy for breast cancer, 30% of the patients who received denosumab were ≥ 65 years old.
In a clinical trial of patients with glucocorticoid-induced osteoporosis, 248 (44.6%) of the female subjects were ≥ 65 years old.
Males
In the male osteoporosis trial, no overall differences in efficacy were observed in patients ≥ 65 years of age (N = 133) who received denosumab, compared with younger patients. However, greater sensitivity of some older individuals cannot be ruled out.
There were 133 patients (55%) ≥ 65 years of age, of whom 39 patients (16%) were ≥ 75 years. The incidence of adverse events (AEs) in patients ≥ 65 and ≥ 75 years of age were 107 events in 50 patients (73.5%) and 30 events in 14 patients (70.0%) in the denosumab group vs. 124 events in 43 patients (67.2%) and 45 events in 12 patients (63.2%) in the placebo group, respectively; the incidence of serious adverse events (SAEs) were 14 events in 10 patients (14.7%) and 5 events in 4 patients (20.0%) in the denosumab group vs. 8 events in 6 patients (9.4%) and 1 event in 1 patient (5.3%) in the placebo group, respectively. The incidence of AEs in patients < 65 years of age were 61 events in 36 patients (69.2%) in the denosumab group vs. 100 events in 41 patients (73.2%) in the placebo group; the incidence of SAEs in patients < 65 years of age were 2 events in 1 patient (1.9%) in the denosumab group vs. 5 events in 4 patients (7.1%) in the placebo group.
In the clinical trial of men with bone loss associated with ADT for nonmetastatic prostate cancer, 93% of the patients who received denosumab were ≥ 65 years old. No overall differences in safety or efficacy were observed between these patients and younger patients.
In a clinical trial of patients with glucocorticoid-induced osteoporosis, 107 (44.8%) of the male subjects were ≥ 65 years old.
For men with sexual partners who could become pregnant, see also Special Populations, Pregnant Women and Special Populations, Males.
Information to be Provided to the Patient
Patients must be adequately supplemented with calcium and vitamin D. All patients should be instructed on the importance of calcium and vitamin D supplementation in maintaining serum calcium levels. Patients should be advised to seek prompt medical attention if they develop signs or symptoms of hypocalcemia (eg, paresthesias or muscle spasms) (see PATIENT MEDICATION INFORMATION).
Patients should be advised to seek prompt medical attention if they develop signs or symptoms of cellulitis.
Patients should be aware of the most commonly associated side effects of Jubbonti therapy.
If a dose of Jubbonti is missed, the injection should be administered as soon as convenient. Thereafter, injections should be scheduled every 6 months from the date of the last injection.
8 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared Jubbonti to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
A total of 8091 women (4050 denosumab vs. 4041 placebo) were enrolled in placebo-controlled studies of women with postmenopausal osteoporosis or low bone mass (Study 1 and Study 2), and a total of 242 men (121 denosumab vs. 121 placebo) were enrolled in a placebo-controlled study of men with osteoporosis (Study 5). A total of 1468 men (734 denosumab vs. 734 placebo) were enrolled in a placebo-controlled study of bone loss in men with nonmetastatic prostate cancer receiving androgen deprivation therapy (ADT) (Study 6). A total of 252 women (127 denosumab vs. 125 placebo) were enrolled in a placebo-controlled study of bone loss in women with breast cancer receiving adjuvant aromatase inhibitor (AI) therapy (Study 7). A total of 795 patients, 70% women and 30% men, (398 denosumab vs. 397 risedronate) were enrolled in an active controlled study of glucocorticoid-induced osteoporosis (Study 8).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful for identifying and approximating rates of adverse drug reactions in real-world use.
Treatment of Postmenopausal Osteoporosis
The safety of denosumab in the treatment of postmenopausal osteoporosis was assessed in a large, 3-year, randomized, double-blind, placebo-controlled, multinational study of 7808 postmenopausal women aged 60 to 91 years with osteoporosis (Study 1). A total of 3876 women received placebo and 3886 women received denosumab administered once every 6 months as a single 60 mg subcutaneous (SC) dose. All women received calcium (at least 1000 mg) and vitamin D (at least 400 IU) supplementation per day.
The incidence of adverse events was 93% in both treatment groups (n = 3605 in the denosumab group and 3607 in the placebo group).
- The 3 most common adverse events overall were back pain (1347 [34.7%] denosumab, 1340 [34.6%] placebo), arthralgia (784 [20.2%] denosumab, 782 [20.2%] placebo), and hypertension (614 [15.8%] denosumab, 636 [16.4%] placebo).
- The most common adverse events (> 5% and more common than placebo) were back pain (1347 [34.7%] denosumab, 1340 [34.6%] placebo), pain in extremity (453 [11.7%] denosumab, 430 [11.1%] placebo), hypercholesterolemia (280 [7.2%] denosumab, 236 [6.1%] placebo), musculoskeletal pain (297 [7.6%] denosumab, 291 [7.5%] placebo) and cystitis (228 [5.9%] denosumab, 225 [5.8%] placebo).
The incidence of serious adverse events was 25.8% (n = 1004) in the denosumab group and 25.1% (n = 972) in the placebo group.
- The 3 most common serious adverse events were osteoarthritis (63 [1.6%] denosumab, 79 [2.0%] placebo), atrial fibrillation (36 [0.9%] denosumab, 33 [0.9%] placebo), and pneumonia (34 [0.9%] denosumab, 36 [0.9%] placebo). Deaths occurred in 70 subjects (1.8%) in the denosumab group and 90 subjects (2.3%) in the placebo group. Adverse events leading to treatment discontinuation occurred in 192 (4.9%) women in the denosumab group and 202 (5.2%) women in the placebo group.
- The 3 most common adverse events leading to treatment discontinuation were breast cancer (including patients with a history of breast cancer) (20 [0.5%] denosumab, 10 [0.3%] placebo), back pain (6 [0.2%] denosumab, 10 [0.3%] placebo), and constipation (6 [0.2%] denosumab, 6 [0.2%] placebo). Cardiac disorders leading to discontinuation were reported in 14 patients (0.4%) in the denosumab group and 3 patients (< 0.1%) in the placebo group.
Adverse events reported in ≥ 1% of postmenopausal women with osteoporosis are shown in Table 2.
| Table 2. Adverse Events Occurring in ≥ 1% of Patients with Postmenopausal Osteoporosis | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 3886) n (%) | Placebo (N = 3876) n (%) | |||
| BLOOD AND LYMPHATIC SYSTEM DISORDERS | |||||
| Anemia | 129 (3.3) | 107 (2.8) | |||
| CARDIAC DISORDERS | |||||
| Angina pectoris | 101 (2.6) | 87 (2.2) | |||
| Atrial fibrillation | 79 (2.0) | 77 (2.0) | |||
| Palpitations | 59 (1.5) | 59 (1.5) | |||
| Cardiac failure | 53 (1.4) | 38 (1.0) | |||
| Arrhythmia | 41 (1.1) | 41 (1.1) | |||
| EAR AND LABYRINTH DISORDERS | |||||
| Vertigo | 195 (5.0) | 187 (4.8) | |||
| Tinnitus | 35 (0.9) | 55 (1.4) | |||
| ENDOCRINE DISORDERS | |||||
| Table 2. Adverse Events Occurring in ≥ 1% of Patients with Postmenopausal Osteoporosis | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 3886) n (%) | Placebo (N = 3876) n (%) | ||||
| Hypothyroidism | 62 (1.6) | 59 (1.5) | ||||
| EYE DISORDERS | ||||||
| Cataract | 229 (5.9) | 253 (6.5) | ||||
| Glaucoma | 59 (1.5) | 64 (1.7) | ||||
| Conjunctivitis | 48 (1.2) | 59 (1.5) | ||||
| GASTROINTESTINAL DISORDERS | ||||||
| Constipation | 355 (9.1) | 361 (9.3) | ||||
| Diarrhea | 228 (5.9) | 236 (6.1) | ||||
| Dyspepsia | 178 (4.6) | 212 (5.5) | ||||
| Nausea | 178 (4.6) | 193 (5.0) | ||||
| Abdominal pain | 146 (3.8) | 149 (3.8) | ||||
| Abdominal pain upper | 129 (3.3) | 111 (2.9) | ||||
| Gastritis | 99 (2.5) | 109 (2.8) | ||||
| Vomiting | 91 (2.3) | 93 (2.4) | ||||
| Flatulence | 84 (2.2) | 53 (1.4) | ||||
| Gastroesophageal reflux disease | 80 (2.1) | 66 (1.7) | ||||
| Hemorrhoids | 55 (1.4) | 50 (1.3) | ||||
| Hiatus hernia | 49 (1.3) | 56 (1.4) | ||||
| GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS | ||||||
| Edema peripheral | 189 (4.9) | 155 (4.0) | ||||
| Fatigue | 115 (3.0) | 127 (3.3) | ||||
| Asthenia | 90 (2.3) | 73 (1.9) | ||||
| Noncardiac chest pain | 84 (2.2) | 90 (2.3) | ||||
| Pain | 47 (1.2) | 55 (1.4) | ||||
| Pyrexia | 45 (1.2) | 40 (1.0) | ||||
| HEPATOBILIARY DISORDERS | ||||||
| Cholelithiasis | 52 (1.3) | 69 (1.8) | ||||
| INFECTIONS AND INFESTATIONS | ||||||
| Nasopharyngitis | 563 (14.5) | 600 (15.5) | ||||
| Influenza | 331 (8.5) | 335 (8.6) | ||||
| Bronchitis | 301 (7.7) | 301 (7.8) | ||||
| Urinary tract infection | 245 (6.3) | 253 (6.5) | ||||
| Cystitis | 228 (5.9) | 225 (5.8) | ||||
| Upper respiratory tract infection | 190 (4.9) | 167 (4.3) | ||||
| Pneumonia | 152 (3.9) | 150 (3.9) | ||||
| Sinusitis | 101 (2.6) | 121 (3.1) | ||||
| Pharyngitis | 91 (2.3) | 78 (2.0) | ||||
| Gastroenteritis | 81 (2.1) | 94 (2.4) | ||||
| Herpes zoster | 79 (2.0) | 72 (1.9) | ||||
| Lower respiratory tract infection | 69 (1.8) | 86 (2.2) | ||||
| Viral infection | 66 (1.7) | 72 (1.9) | ||||
| Rhinitis | 63 (1.6) | 84 (2.2) | ||||
| Respiratory tract infection | 55 (1.4) | 69 (1.8) | ||||
| Ear infection | 43 (1.1) | 21 (0.5) | ||||
| Table 2. Adverse Events Occurring in ≥ 1% of Patients with Postmenopausal Osteoporosis | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 3886) n (%) | Placebo (N = 3876) n (%) | ||||
| Tooth infection | 26 (0.7) | 41 (1.1) | ||||
| INJURY, POISONING AND PROCEDURAL COMPLICATIONS | ||||||
| Fall | 205 (5.3) | 250 (6.4) | ||||
| Contusion | 162 (4.2) | 192 (5.0) | ||||
| Radius fracture | 104 (2.7) | 116 (3.0) | ||||
| Joint sprain | 60 (1.5) | 65 (1.7) | ||||
| Procedural pain | 57 (1.5) | 54 (1.4) | ||||
| Humerus fracture | 42 (1.1) | 49 (1.3) | ||||
| Rib fracture | 40 (1.0) | 33 (0.9) | ||||
| Ulna fracture | 37 (1.0) | 39 (1.0) | ||||
| Foot fracture | 34 (0.9) | 39 (1.0) | ||||
| Lumbar vertebral fracture | 25 (0.6) | 72 (1.9) | ||||
| Thoracic vertebral fracture | 22 (0.6) | 53 (1.4) | ||||
| INVESTIGATIONS | ||||||
| Weight decreased | 41 (1.1) | 49 (1.3) | ||||
| METABOLISM AND NUTRITION DISORDERS | ||||||
| Hypercholesterolemia | 280 (7.2) | 236 (6.1) | ||||
| Diabetes mellitus | 62 (1.6) | 58 (1.5) | ||||
| Hyperlipidemia | 45 (1.2) | 35 (0.9) | ||||
| MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS | ||||||
| Back pain | 1347 (34.7) | 1340 (34.6) | ||||
| Arthralgia | 784 (20.2) | 782 (20.2) | ||||
| Pain in extremity | 453 (11.7) | 430 (11.1) | ||||
| Osteoarthritis | 436 (11.2) | 442 (11.4) | ||||
| Musculoskeletal pain | 297 (7.6) | 291 (7.5) | ||||
| Muscle spasms | 167 (4.3) | 182 (4.7) | ||||
| Bone pain | 142 (3.7) | 117 (3.0) | ||||
| Neck pain | 129 (3.3) | 136 (3.5) | ||||
| Myalgia | 114 (2.9) | 94 (2.4) | ||||
| Spinal osteoarthritis | 82 (2.1) | 64 (1.7) | ||||
| Musculoskeletal chest pain | 61 (1.6) | 63 (1.6) | ||||
| Tendonitis | 56 (1.4) | 47 (1.2) | ||||
| Joint swelling | 55 (1.4) | 66 (1.7) | ||||
| Arthritis | 48 (1.2) | 53 (1.4) | ||||
| NERVOUS SYSTEM DISORDERS | ||||||
| Headache | 237 (6.1) | 258 (6.7) | ||||
| Dizziness | 217 (5.6) | 218 (5.6) | ||||
| Sciatica | 178 (4.6) | 149 (3.8) | ||||
| Syncope | 67 (1.7) | 71 (1.8) | ||||
| Paresthesia | 63 (1.6) | 56 (1.4) | ||||
| Memory impairment | 52 (1.3) | 37 (1.0) | ||||
| PSYCHIATRIC DISORDERS | ||||||
| Depression | 213 (5.5) | 221 (5.7) | ||||
| Insomnia | 126 (3.2) | 122 (3.1) | ||||
| Table 2. Adverse Events Occurring in ≥ 1% of Patients with Postmenopausal Osteoporosis | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 3886) n (%) | Placebo (N = 3876) n (%) | ||||
| Anxiety | 123 (3.2) | 123 (3.2) | ||||
| RENAL AND URINARY DISORDERS | ||||||
| Urinary incontinence | 39 (1.0) | 40 (1.0) | ||||
| Renal cyst | 23 (0.6) | 39 (1.0) | ||||
| RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS | ||||||
| Cough | 224 (5.8) | 238 (6.1) | ||||
| Dyspnea | 93 (2.4) | 105 (2.7) | ||||
| Asthma | 66 (1.7) | 65 (1.7) | ||||
| Pharyngolaryngeal pain | 52 (1.3) | 67 (1.7) | ||||
| Chronic obstructive pulmonary disease | 38 (1.0) | 39 (1.0) | ||||
| SKIN AND SUBCUTANEOUS TISSUE DISORDERS | ||||||
| Rash | 96 (2.5) | 79 (2.0) | ||||
| Pruritus | 87 (2.2) | 82 (2.1) | ||||
| Eczema | 50 (1.3) | 25 (0.6) | ||||
| Alopecia | 31 (0.8) | 41 (1.1) | ||||
| VASCULAR DISORDERS | ||||||
| Hypertension | 614 (15.8) | 636 (16.4) | ||||
| Varicose vein | 58 (1.5) | 60 (1.5) | ||||
| Hematoma | 38 (1.0) | 51 (1.3) | ||||
N = Number of subjects who received ≥ 1 dose of investigational product
n = Number of subjects reporting ≥ 1 event
Includes only treatment-emergent adverse events
Hypocalcemia
In postmenopausal women with osteoporosis in Study 1, declines of serum calcium concentrations to less than the normal range were reported in 15 (0.4%) women in the placebo group and 63 (1.6%) women in the denosumab group. Declines of serum calcium concentrations to < 7.5 mg/dL (< 1.88 mmol/L) were reported in 2 (< 0.1%) women in the placebo group and 1 (< 0.1%) in the denosumab group. In clinical studies, subjects with impaired renal function were more likely to have greater reductions in serum calcium levels compared to subjects with normal renal function. In a study of 55 patients with varying degrees of renal function who did not receive calcium and vitamin D supplementation, symptomatic hypocalcemia or serum calcium levels < 7.5 mg/dL was observed in 5 subjects, including no subjects in the normal renal function group, 10% (1 out of 10) of subjects in the CrCL 50 to 80 mL/min group, 29% (2 out of 7) of subjects in the CrCL < 30 mL/min group, and 29% (2 out of 7) of subjects in the hemodialysis group (see 7 WARNINGS AND PRECAUTIONS).
Infections
Receptor activator of nuclear factor kappa-B ligand (RANKL) is expressed on activated T and B lymphocytes and in lymph nodes. Therefore, a RANKL inhibitor such as denosumab may increase the risk of infection. In the clinical study of 7808 postmenopausal women with osteoporosis, the incidence of infections resulting in death was 6 (0.2%) in both placebo and denosumab treatment groups. The incidence of nonfatal serious infections was 3.3% (n = 128) in the placebo group and 4.0% (n = 154) in the denosumab group. Hospitalizations due to serious infections in the abdomen 28 (0.7%) placebo vs. 36 (0.9%) denosumab, urinary tract 20 (0.5%) placebo vs. 29 (0.7%) denosumab, and ear 0 (0.0%) placebo vs. 5 (0.1%) denosumab were reported. Endocarditis was reported in 0 (0.0%) placebo patients and 3 (0.1%) patients receiving denosumab.
Overall skin infections leading to hospitalization were reported more frequently in patients treated with denosumab (2 [< 0.1%] placebo vs. 15 [0.4%] denosumab) among women with postmenopausal osteoporosis in Study 1. These events were predominantly comprised of erysipelas (0 [0%] placebo and 7 [0.2%] denosumab) and cellulitis (1 [< 0.1%] placebo and 6 [0.2%] denosumab) (see 7 WARNINGS AND PRECAUTIONS).
The overall incidence of infections was similar between the denosumab and placebo groups (2055 [52.9%] denosumab, 2108 [54.4%] placebo). The incidence of specific infection types was as follows: urinary tract infections (245 [6.3%] denosumab, 253 [6.5%] placebo), upper respiratory infections (190 [4.9%] denosumab, 167 [4.3%] placebo), ear infections (43 [1.1%] denosumab, 21 [0.5%] placebo), and diverticulitis (28 [0.7%] denosumab, 22 [0.6%] placebo).
There was no imbalance in the reporting of opportunistic infections (4 [0.1%] denosumab, 3 [0.1%] placebo).
Skin
A significantly higher number of patients treated with denosumab developed epidermal and dermal adverse events (such as dermatitis, eczema, and rashes), with these events reported in 8.2% (n = 316) of placebo and 10.8% (n = 421) of denosumab group (p < 0.0001). Most of these events were not specific to the injection site (see 7 WARNINGS AND PRECAUTIONS, Skin).
Osteonecrosis of the Jaw (ONJ)
ONJ has been reported rarely in the open-label osteoporosis clinical trial program in patients treated with denosumab (see 7 WARNINGS AND PRECAUTIONS).
Atypical Femoral Fracture
In the osteoporosis clinical trial program, atypical femoral fractures were reported in patients treated with denosumab (see 7 WARNINGS AND PRECAUTIONS).
Multiple Vertebral Fractures (MVF) Following Treatment Discontinuation
In the osteoporosis clinical trial program, MVF were reported in patients following discontinuation of treatment with denosumab, particularly in those with a history of vertebral fracture.
Cardiovascular Disorders
The incidence of positively adjudicated cardiovascular serious adverse events was 186 (4.8%) denosumab and 178 (4.6%) placebo, with a hazard ratio (95% confidence interval) of 1.02
(0.83, 1.25). Adjudicated cardiovascular events were further sub-categorized as follows: cardiovascular death, acute coronary syndrome, stroke/transient ischemic attack, congestive heart failure, other vascular event, and arrhythmia. The incidence of these subcategories was 23 (0.6%) denosumab and 31 (0.8%) placebo for cardiovascular death, 47 (1.2%) denosumab and 39 (1.0%) placebo for acute coronary syndrome, 56 (1.4%) denosumab and 54 (1.4%) placebo for stroke/transient ischemic attack, 27 (0.7%) denosumab and 22 (0.6%) placebo for congestive heart failure, 31 (0.8%) denosumab and 30 (0.8%) placebo for other vascular event, and 52 (1.3%) denosumab and 45 (1.2%) placebo for arrhythmia.
Fracture Healing
Delayed fracture healing of nonvertebral fractures was reported in 2 out of 303 (0.7%) subjects in the denosumab group (3 out of 386 [0.8%] nonvertebral fractures) and 2 out of 364 (0.5%) subjects in the placebo group (2 out of 465 [0.4%] nonvertebral fractures). In addition, non union of nonvertebral fractures was reported in 0 out of 303 (0%) subjects in the denosumab group (0 out of 386 [0%] nonvertebral fractures) and 1 out of 364 (0.3%) subjects in the placebo group (1 out of 465 [0.2%] nonvertebral fractures). For fractures that occurred near the final study closure, additional follow-up after study closure identified 2 additional subjects in the placebo group and 0 in the denosumab group with delayed fracture healing. Of the subjects with a distal radius fracture, 1 out of 104 (1.0%) subjects in the denosumab group (1 out of 106 [0.9%] distal radius fractures) and 0 out of 116 (0%) subjects in the placebo group (0 out of 118 [0%] distal radius fractures) had delayed fracture healing.
Malignancies
The overall incidence of new malignancies was 188 (4.8%) in the denosumab and 166 (4.3%) in the placebo groups. The most common malignancies (≥ 0.2%) included: breast cancer (28 [0.7%] denosumab, 26 [0.7%] placebo), colon cancer (11 [0.3%] denosumab, 8 [0.2%] placebo), lung neoplasm malignant (9 [0.2%] denosumab, 9 [0.2%] placebo), gastric cancer (7 [0.2%] denosumab, 3 [0.1%] placebo), pancreatic carcinoma (7 [0.2%] denosumab, 3 [0.1%] placebo), squamous cell carcinoma of skin (6 [0.2%] denosumab, 8 [0.2%] placebo), and recurrent breast cancer (6 [0.2%] denosumab, 2 [0.1%] placebo). Other malignancies reported include: thyroid cancer (2 [0.1%] denosumab, 0 [0%] placebo), carcinoid of the stomach (1 [< 0.1%] denosumab, 0 [0%] placebo), uterine cancer (3 [0.1%] denosumab, 1 [< 0.1%] placebo), ovarian cancer metastatic (2 [0.1%] denosumab, 0 [0%] placebo), ovarian epithelial cancer (2 [0.1%] denosumab, 0 [0%] placebo), vulval cancer (2 [0.1%] denosumab, 0 [0%] placebo), and lentigo maligna stage unspecified (3 [0.1%] denosumab, 0 [0%] placebo). A causal relationship to drug exposure has not been established.
Hypersensitivity Reactions
The incidence of adverse drug reactions potentially associated with hypersensitivity was 50 (1.3%) in the denosumab group and 50 (1.3%) in the placebo group. The most common adverse event potentially associated with hypersensitivity was urticaria (27 [0.7%] denosumab, 27 [0.7%] placebo).
Pancreatitis
Pancreatitis was reported in 4 patients (0.1%) in the placebo and 8 patients (0.2%) in the denosumab groups. Of these reports, one patient in the placebo group and all 8 patients in the denosumab group had serious events including 2 deaths in the denosumab group. Several patients had a prior history of pancreatitis or a confounding event (eg, gallstones). The time from product administration to event occurrence was variable.
Laboratory Abnormalities
The most frequent laboratory abnormalities were changes in serum calcium with compensatory physiological changes in serum phosphorus. The median percent change from baseline (interquartile range) at month 1 for serum calcium was -2.1% (-5.2% to 1.0%) for denosumab and 1.0% (-2.0% to 3.2%) for placebo. The median percent change from baseline (interquartile range) at month 1 for serum phosphorus was -8.3% (-15.8% to 0%) for denosumab and 0% (-5.6% to 8.3%) for placebo. Alkaline phosphatase was also reduced, by month 6, which reflects reduced osteoclast activity in bone, with a decrease from baseline of 25% in denosumab subjects compared to 3% to 8% in placebo subjects.
Serum phosphorous levels were between 2.0 and 2.5 mg/dL in 2.0% (n = 82) of patients in the placebo group and 7.0% (n = 263) of patients in the denosumab group. Decrease in platelet levels to between 50,000/mm3 and 75,000/mm3 was reported at 0.2% (n = 7) in the placebo group and 0.4% (n = 14) in the denosumab group, and decrease in platelet levels to < 25,000/mm3 was reported at < 0.1% (n = 2) in the placebo group and at 0.1% (n = 4) in the denosumab group. Increase in aspartate aminotransferase (AST) levels to between 1.0 and 2.5 x the upper limit of normal (ULN) was reported at 5.0% (n = 206) in the placebo group and 7.0% (n = 264) in the denosumab group, and increase in alanine aminotransferase levels (ALT) to between 2.5 and 5.0 x ULN were reported at 0.5% (n = 21) in the placebo group and 1.0% (n = 37) in the denosumab group. Increase in total bilirubin value to between 3.0 and 10.0 x ULN was reported at 0.0% (n = 0) in the placebo group and 0.1% (n = 5) in the denosumab group.
Long Term Safety in Postmenopausal Osteoporosis
The safety of denosumab was assessed in clinical studies of up to 10 years in duration.
A total of 4550 patients who completed Study 1 (N = 7808) enrolled into a 7-year, multinational, multicenter, open label, single-arm extension study to evaluate the long-term safety and efficacy of denosumab. All patients in the extension study were to receive denosumab every 6 months as a single 60 mg SC dose, as well as daily calcium (1 g) and vitamin D (at least 400 IU).
Based on data from 7 years of the extension study for patients who received denosumab in Study 1 and continued on therapy (years 4 through 10 of denosumab treatment; N = 2343), the overall subject incidence rates of adverse events and serious adverse events reported (event rates per 100 patient-years) were similar to that observed in the initial 3 years of Study 1. For patients who crossed over to denosumab from placebo in Study 1 (N = 2206), the overall subject incidence rates of adverse events and serious adverse events reported (event rates per 100 patient-years) were also similar to that observed in the first 3 years of Study 1. Events of osteonecrosis of the jaw and atypical femoral fractures have been observed.
A summary of the safety results are provided in the following Table 3.
Patient-year = Total patient-years of follow-up, including time through the end of study date; Events = Number of events; Rate = Event rate per 100 patient-years ([Events / Patient-year] * 100)
N = Number of patients who received ≥ 1 dose of investigational product. Treatment groups in Extension are based on the original randomized assignments in the 20030216 study.
Multiple occurrences of the same event for a patient are counted as multiple events. Includes only treatment -emergent adverse events.
| Table 3. Patient-year-adjusted Adverse Events Rates (per 100 Patient-years) | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Placebo | Denosumab | |||||||||||||||||
Study 1 Years 1-3 N = 3883 (Patient-year = 10738.8) Rate (Events) | Study 1 Years 1-3 N = 3879 (Patient-year = 10805.6) Rate (Events) | Cross-Over Extension Years 1-7 N = 2206 (Patient-year = 12082.7) Rate (Events) | Long-Term Extension Years 4-10 N = 2343 (Patient-year = 12798.0) Rate (Events) | |||||||||||||||
| All Adverse Events (AE) | 237.3 (25482) | 235.1 (25406) | 174.5 (21083) | 174.8 (22374) | ||||||||||||||
| Most Common AEs | ||||||||||||||||||
| Arthralgia | 10.2 (1093) | 10.3 (1112) | 6.3 (765) | 6.1 (778) | ||||||||||||||
| Back Pain | 19.1 (2052) | 19.0 (2053) | 5.9 (710) | 5.3 (676) | ||||||||||||||
| Hypertension | 6.7 (723) | 6.5 (701) | 5.0 (604) | 4.9 (629) | ||||||||||||||
| Nasopharyngitis | 7.3 (782) | 7.0 (751) | 4.7 (565) | 4.5 (576) | ||||||||||||||
| Osteoarthritis | 5.5 (587) | 4.8 (519) | 4.4 (536) | 4.7 (602) | ||||||||||||||
| Pain in extremity | 5.2 (555) | 5.6 (600) | 2.8 (338) | 3.0 (389) | ||||||||||||||
| Serious Adverse Events | 16.4 (1758) | 17.3 (1870) | 17.2 (2080) | 17.3 (2217) | ||||||||||||||
| Deaths | 0.9 (92) | 0.7 (72) | 0.8 (102) | 0.9 (111) | ||||||||||||||
| Clinically Significant AEs | ||||||||||||||||||
| Hypocalcemia | <0.1 (3) | 0 (0) | <0.1 (10) | <0.1 (6) | ||||||||||||||
| Osteonecrosis of the Jaw | 0 (0) | 0 (0) | <0.1 (6) | <0.1 (7) | ||||||||||||||
| Atypical Femoral Fracture | 0 (0) | 0 (0) | <0.1 (1) | <0.1 (1) | ||||||||||||||
| Serious Infections | 1.4 (152) | 1.8 (191) | 1.9 (230) | 2.0 (253) | ||||||||||||||
| Infections | 40.9 (4396) | 40.6 (4385) | 32.7 (3948) | 33.6 (4296) | ||||||||||||||
| Malignancies | 1.8 (191) | 1.9 (210) | 2.4 (291) | 2.2 (287) | ||||||||||||||
| Delayed Fracture Healing | <0.1 (2) | <0.1 (1) | 0 (0.0) | <0.1 (1) | ||||||||||||||
| Pancreatitis | <0.1 (3) | <0.1 (9) | <0.1 (5) | <0.1 (11) | ||||||||||||||
| Eczema | 0.7 (77) | 1.3 (139) | 1.1 (129) | 1.0 (131) | ||||||||||||||
| Hypersensitivity | 3.2 (347) | 4.2 (457) | 3.0 (359) | 2.9 (370) | ||||||||||||||
Other Studies in Postmenopausal Women
The safety of denosumab was assessed in a 2-year, randomized, double-blind, placebo-controlled, multinational study of 332 postmenopausal women aged 43 to 83 years with low bone mass (Study 2). A total of 165 women received placebo and 164 women received denosumab administered once every 6 months as a single 60 mg SC dose. All women received calcium (at least 1000 mg) and vitamin D (at least 400 IU) supplementation per day. The incidence of adverse events was 156 (95%) in the denosumab group and 157 (95%) in the placebo group. The incidence of serious adverse events was 11% (n = 18) in the denosumab group and 6% (n = 9) in the placebo group. No subject died during the study. The 3 most common adverse events were arthralgia (26% (n = 43) denosumab vs. 26% (n = 42) placebo), nasopharyngitis (22% (n = 36) denosumab vs. 19% (n = 32) placebo), and back pain (20% (n = 33) denosumab vs. 21% (n = 34) placebo).
Two randomized, double-blind, active-controlled studies (Study 3 and Study 4) assessed the safety of denosumab compared with alendronate. In Study 3, a total of 1179 postmenopausal women with low bone mass who were treatment naive (593 randomized to denosumab 60 mg SC once every 6 months, 586 randomized to alendronate tablets 70 mg once weekly) received investigational product and were evaluated for safety. All women received daily supplemental calcium (at least 1000 mg) and vitamin D (at least 400 IU). The incidence of adverse events was 81% (n = 480) in the denosumab group and 82% (n = 482) in the alendronate group. The incidence of serious adverse events was 6% (n = 34) in the denosumab group and 6% (n = 37) in the alendronate group. One subject in each treatment group died during the study. The 3 most frequent adverse events were arthralgia (13% (n = 75) denosumab vs. 10% (n = 56) alendronate), nasopharyngitis (8% (n = 45) denosumab vs. 7% (n = 43) alendronate), and back pain (7% (n = 42) denosumab vs. 10% (n = 56) alendronate).
In Study 4, a total of 502 postmenopausal women with low bone mass who were being treated with alendronate for a median duration of 3 years (253 denosumab 60 mg SC every 6 months, 249 alendronate tablets 70 mg once weekly) received investigational product and were evaluated for safety. All women received daily supplemental calcium (at least 1000 mg) and vitamin D (at least 400 IU). The incidence of adverse events was 78% (n = 197) in the denosumab group and 79% (n = 196) in the alendronate group. The incidence of serious adverse events was 6% (n = 15) in the denosumab group and 6% (n = 16) in the alendronate group. One subject in the denosumab treatment group died during the study. The 3 most frequent adverse events were nasopharyngitis (13% (n = 34) denosumab vs. 11% (n = 27) alendronate), back pain (11% (n = 27) denosumab vs. 12% (n = 29) alendronate), and arthralgia (6% (n = 15) denosumab vs. 10% (n = 26) alendronate).
The safety profile of denosumab in women with postmenopausal osteoporosis was consistent with results in these 3 studies among women with postmenopausal bone loss. No notable differences were observed between those women who had received prior osteoporosis therapy versus those who had not received prior osteoporosis therapy (ie, alendronate).
Immunogenicity
Denosumab is a human monoclonal antibody. As with all therapeutic proteins, there is potential for immunogenicity with Jubbonti. More than 13000 patients were screened for binding antibodies using a sensitive electro chemiluminescent bridging immunoassay. Less than 1% (55 out of 8113) of patients treated with denosumab for up to 5 years tested positive for antibodies (including pre-existing, transient, and developing antibodies). The patients that tested positive for binding antibodies were further evaluated for neutralizing antibodies using a chemiluminescent cell-based in vitro biological assay and none of them tested positive. No evidence of altered pharmacokinetic profile, toxicity profile, or clinical response was associated with binding antibody development.
The detection of antibody formation is dependent on the sensitivity and specificity of the assay. The observed incidence of antibody positivity in an assay may be influenced by factors such as sample handling, concomitant medications, and underlying disease. For these reasons, comparison of antibodies to denosumab with the incidence of antibodies to other products may be misleading.
Treatment to Increase Bone Mass in Men with Osteoporosis at High Risk for Fracture
The safety of denosumab in the treatment of men with osteoporosis was assessed in a randomized, double-blind, placebo-controlled study; a 1 year double-blind phase followed by a 1 year open-label extension.
During the double-blind phase, a total of 242 men (121 denosumab, 121 placebo) were enrolled; a total of 120 men were exposed to placebo and 120 men were exposed to denosumab administered subcutaneously once every 6 months as a single 60 mg dose. All men were instructed to take at least 1000 mg of calcium and 800 IU of vitamin D supplementation per day.
The most common adverse reactions (≥ 5% and more common than placebo) reported in men with osteoporosis were: back pain (10 [8.3%] denosumab, 8 [6.7%] placebo), arthralgia (8 [6.7%] denosumab, 7 [5.8%] placebo), and nasopharyngitis (8 [6.7%] denosumab, 7 [5.8%] placebo).
There were 2 deaths during the clinical trial: 1 (0.8%, acute myocardial infarction) in the denosumab group and 1 (0.8%, basilar artery thrombosis) in the placebo group.
There were 16 serious adverse events (SAEs) in 11 patients (9.2%) in the denosumab group: 6 cardiovascular (2 arterial thrombosis limb, 2 myocardial infarction, 1 peripheral ischemia, 1 vascular pseudoaneurysm), 3 prostate cancer, and one each of: chest pain, acute pancreatitis, cholecystitis, injury, post procedural complication, road traffic accident, spinal column stenosis (severity: 3 moderate, 12 severe, and 1 fatal). In the placebo group, there were 13 SAEs in 10 patients (8.3%): 3 cardiovascular (peripheral ischemia, atrial fibrillation, basilar artery thrombosis), 3 musculoskeletal (ligament rupture, meniscus lesion, osteoarthritis), 2 ophthalmic (retinal detachment, vitreous hemorrhage), and one each of: pancreatitis, pneumonia, prostatic adenoma, skull malformation, and cerebral hemorrhage (severity: 2 mild, 8 moderate, 2 severe, and 1 fatal).
The number (percentage) of patients who discontinued the investigational product or withdrew from the study due to adverse events was 4 patients (3.3%) with 4 events for the denosumab group (prostate cancer, myocardial infarction, upper respiratory tract infections, and road traffic accident), vs. 0 for the placebo group.
Adverse events reported in ≥ 1% of denosumab-treated or placebo-treated patients are shown in Table 4.
| Table 4. Adverse Events Occurring in ≥ 1% of Men with Osteoporosis (First 12 Months Analysis) | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 120) n (%) | Placebo (N = 120) n (%) | |||
| CARDIAC DISORDERS | |||||
| Angina pectoris | 2 (1.7) | 0 (0.0) | |||
| Arrhythmia | 2 (1.7) | 0 (0.0) | |||
| Atrial fibrillation | 0 (0.0) | 2 (1.7) | |||
| EYE DISORDERS | |||||
| Cataract | 2 (1.7) | 3 (2.5) | |||
| Conjunctivitis | 0 (0.0) | 2 (1.7) | |||
| GASTROINTESTINAL DISORDERS | |||||
| Diarrhea | 2 (1.7) | 3 (2.5) | |||
| Flatulence | 2 (1.7) | 0 (0.0) | |||
| Gastroesophageal reflux disease | 1 (0.8) | 2 (1.7) | |||
| Constipation | 0 (0.0) | 7 (5.8) | |||
| Abdominal pain upper | 0 (0.0) | 3 (2.5) | |||
| Dyspepsia | 0 (0.0) | 2 (1.7) | |||
| Gastric polyps | 0 (0.0) | 2 (1.7) | |||
| Inguinal hernia | 0 (0.0) | 2 (1.7) | |||
| GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS | |||||
| Chest pain | 2 (1.7) | 1 (0.8) | |||
| Fatigue | 1 (0.8) | 2 (1.7) | |||
| INFECTIONS AND INFESTATIONS | |||||
| Nasopharyngitis | 8 (6.7) | 7 (5.8) | |||
| Sinusitis | 2 (1.7) | 1 (0.8) | |||
| Tooth infection | 2 (1.7) | 1 (0.8) | |||
| Upper respiratory tract infection | 2 (1.7) | 1 (0.8) | |||
| Influenza | 1 (0.8) | 4 (3.3) | |||
| Pneumonia | 0 (0.0) | 2 (1.7) | |||
| INJURY, POISONING AND PROCEDURAL COMPLICATIONS | |||||
| Fall | 2 (1.7) | 2 (1.7) | |||
| Contusion | 2 (1.7) | 0 (0.0) | |||
| Post procedural hematoma | 1 (0.8) | 2 (1.7) | |||
| Procedural pain | 0 (0.0) | 3 (2.5) | |||
| Arthropod bite | 0 (0.0) | 2 (1.7) | |||
| INVESTIGATIONS | |||||
| Weight decreased | 0 (0.0) | 2 (1.7) | |||
| METABOLISM AND NUTRITION DISORDERS | |||||
| Hypercholesterolemia | 3 (2.5) | 0 (0.0) | |||
| Hyperglycemia | 0 (0.0) | 2 (1.7) | |||
| Table 4. Adverse Events Occurring in ≥ 1% of Men with Osteoporosis (First 12 Months Analysis) | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 120) n (%) | Placebo (N = 120) n (%) | |||
| Hyponatremia | 0 (0.0) | 2 (1.7) | |||
| MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS | |||||
| Back pain | 10 (8.3) | 8 (6.7) | |||
| Arthralgia | 8 (6.7) | 7 (5.8) | |||
| Osteoarthritis | 4 (3.3) | 2 (1.7) | |||
| Muscle spasms | 3 (2.5) | 0 (0.0) | |||
| Myalgia | 2 (1.7) | 5 (4.2) | |||
| Pain in extremity | 2 (1.7) | 3 (2.5) | |||
| Bone pain | 2 (1.7) | 0 (0.0) | |||
| Musculoskeletal pain | 1 (0.8) | 4 (3.3) | |||
| Musculoskeletal chest pain | 1 (0.8) | 2 (1.7) | |||
| Musculoskeletal stiffness | 0 (0.0) | 2 (1.7) | |||
| Spinal osteoarthritis | 0 (0.0) | 2 (1.7) | |||
| NEOPLASMS BENIGN, MALIGNANT AND UNSPECIFIED (INCLUDING CYSTS AND POLYPS) | |||||
| Prostate cancera | 3 (2.5) | 0 (0.0) | |||
| Prostatic adenoma | 1 (0.8) | 2 (1.7) | |||
| NERVOUS SYSTEM DISORDERS | |||||
| Dizziness | 2 (1.7) | 2 (1.7) | |||
| Headache | 1 (0.8) | 5 (4.2) | |||
| RENAL AND URINARY DISORDERS | |||||
| Renal cyst | 0 (0.0) | 2 (1.7) | |||
| RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS | |||||
| Cough | 1 (0.8) | 3 (2.5) | |||
| Asthma | 0 (0.0) | 2 (1.7) | |||
| SKIN AND SUBCUTANEOUS TISSUE DISORDERS | |||||
| Rash | 1 (0.8) | 2 (1.7) | |||
| VASCULAR DISORDERS | |||||
| Arterial thrombosis limb | 2 (1.7) | 0 (0.0) | |||
| Hypertension | 1 (0.8) | 5 (4.2) | |||
N = Number of subjects who received ≥ 1 dose of investigational product
n = Number of subjects reporting ≥ 1 event
Includes only treatment-emergent adverse events
a2 of the prostate cancer cases were diagnosed within the first month of the patients receiving denosumab
Osteonecrosis of the Jaw
Osteonecrosis of the jaw (ONJ) has been reported in patients treated with denosumab or bisphosphonates, another class of anti-resorptive agents (see 7 WARNINGS AND PRECAUTIONS, Osteonecrosis of the Jaw).
New Malignancies
New malignancies were reported in 4 patients (3.3%; 3 prostate cancers, 1 basal cell carcinoma) in the denosumab group and 0 in the placebo group.
Cardiac Disorders
There were 6 patients (5.0%) with cardiac AEs (2 angina pectoris, 2 myocardial infarction and 2 arrhythmia) in the denosumab group, and 3 patients (2.5%, 2 atrial fibrillation and 1 palpitations) in the placebo group. There were 2 patients (1.7%) with serious cardiac AEs (2 myocardial infarction) in the denosumab group, and 1 (0.8%, atrial fibrillation) in the placebo group.
Fracture
Clinical fractures were confirmed for 1 patient (0.8%) in the denosumab group and 2 patients (1.7%) in the placebo group; new morphometric vertebral fractures were confirmed in no patients in the denosumab group and 1 patient (0.8%) in the placebo group.
Laboratory Abnormalities
Denosumab administration was associated with decreases in serum calcium. At day 15, median change from baseline in albumin-adjusted serum calcium was -1.1% in the denosumab group and 0.0% in the placebo group. No decrease in median serum calcium was observed at months 6 and 12. No patients had Grade 3 or 4 low serum calcium values during the study.
Denosumab administration also was associated with decreases in serum phosphorus. Median change from baseline in phosphorus was (denosumab, placebo) -6.0%, 2.9% at day 15; -4.7%, 0.0% at month 6; and 0.0%, 0.0% at month 12. No patients had Grade 3 or 4 low serum phosphorus values during the study.
Treatment to Increase Bone Mass in Patients Receiving ADT for Prostate Cancer
The safety of denosumab in the treatment of bone loss in men with nonmetastatic prostate cancer receiving ADT was assessed in a 3 year, randomized, double-blind, placebo-controlled, multinational study.
During the double-blind phase, a total of 1468 men aged 48 to 97 years were enrolled; the median age was 76 years, and 92.9% of subjects were ≥ 65 years of age. A total of 725 men were exposed to placebo and 731 men were exposed to denosumab administered once every 6 months as a single 60 mg subcutaneous dose. All men were instructed to take at least 1000 mg of calcium and 400 IU of vitamin D supplementation per day.
Adverse events reported in ≥ 5% of denosumab-treated patients receiving ADT for nonmetastatic prostate cancer, and more frequently than in the placebo-treated patients were (denosumab vs. placebo): arthralgia (92 [12.6%] denosumab, 80 [11.0%] placebo), back pain (81 [11.1%] denosumab, 74 [10.2%] placebo), pain in extremity (66 [9.0%] denosumab, 51 [7.0%] placebo), hypertension (57 [7.8%] denosumab, 51 [7.0%] placebo), edema peripheral (53 [7.3%] denosumab, 48 [6.6%] placebo), nasopharyngitis (47 [6.4%] denosumab, 45 [6.2%] placebo), dizziness (41 [5.6%] denosumab, 31 [4.3%] placebo), musculoskeletal pain (41 [5.6%] denosumab, 26 [3.6%] placebo), diarrhea (40 [5.5%] denosumab, 39 [5.4%] placebo), hot flush (38 [5.2%] denosumab, 32 [4.4%] placebo), and urinary tract infection (37 [5.1%] denosumab, 32 [4.4%] placebo).
The incidence of SAEs was 34.6% (n = 253) in the denosumab group and 30.6% (n = 222) in the placebo group. The 3 most common serious adverse events were myocardial infarction (14 [1.9%] denosumab, 18 [2.5%] placebo), pneumonia (11 [1.5%] denosumab, 11 [1.5%] placebo), and atrial fibrillation (11 [1.5%] denosumab, 8 [1.1%] placebo). Deaths occurred in 44 subjects (6.0%) in the denosumab group and 46 subjects (6.3%) in the placebo group.
The percentage of patients who withdrew from the study due to adverse events was 51 (7.0%) and 44 (6.1%) for the denosumab and placebo groups, respectively.
Adverse events reported in ≥ 1% of denosumab-treated or placebo-treated patients are shown in Table 5.
| Table 5. Adverse Events Occurring in ≥ 1% of Men with Bone Loss Associated with ADT for Nonmetastatic Prostate Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 731) n (%) | Placebo (N = 725) n (%) | ||||
| BLOOD AND LYMPHATIC SYSTEM DISORDERS | ||||||
| Anemia | 33 (4.5) | 35 (4.8) | ||||
| CARDIAC DISORDERS | ||||||
| Atrial fibrillation | 21 (2.9) | 18 (2.5) | ||||
| Angina pectoris | 17 (2.3) | 8 (1.1) | ||||
| Coronary artery disease | 15 (2.1) | 17 (2.3) | ||||
| Myocardial infarction | 14 (1.9) | 18 (2.5) | ||||
| Cardiac failure congestive | 13 (1.8) | 18 (2.5) | ||||
| Bradycardia | 8 (1.1) | 4 (0.6) | ||||
| EAR AND LABYRINTH DISORDERS | ||||||
| Vertigo | 13 (1.8) | 9 (1.2) | ||||
| ENDOCRINE DISORDERS | ||||||
| Hypothyroidism | 9 (1.2) | 2 (0.3) | ||||
| EYE DISORDERS | ||||||
| Cataract | 34 (4.7) | 9 (1.2) | ||||
| GASTROINTESTINAL DISORDERS | ||||||
| Constipation | 73 (10.0) | 75 (10.3) | ||||
| Diarrhea | 40 (5.5) | 39 (5.4) | ||||
| Nausea | 22 (3.0) | 27 (3.7) | ||||
| Abdominal pain | 15 (2.1) | 21 (2.9) | ||||
| Gastroesophageal reflux disease | 12 (1.6) | 13 (1.8) | ||||
| Gastritis | 11 (1.5) | 8 (1.1) | ||||
| Inguinal hernia | 11 (1.5) | 4 (0.6) | ||||
| Vomiting | 11 (1.5) | 17 (2.3) | ||||
| Dyspepsia | 10 (1.4) | 13 (1.8) | ||||
| Abdominal pain upper | 9 (1.2) | 12 (1.7) | ||||
| Rectal hemorrhage | 7 (1.0) | 9 (1.2) | ||||
| GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS | ||||||
| Edema peripheral | 53 (7.3) | 48 (6.6) | ||||
| Fatigue | 44 (6.0) | 45 (6.2) | ||||
| Asthenia | 31 (4.2) | 27 (3.7) | ||||
| Pyrexia | 11 (1.5) | 10 (1.4) | ||||
| Chest pain | 8 (1.1) | 10 (1.4) | ||||
| Non-cardiac chest pain | 8 (1.1) | 8 (1.1) | ||||
| Table 5. Adverse Events Occurring in ≥ 1% of Men with Bone Loss Associated with ADT for Nonmetastatic Prostate Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 731) n (%) | Placebo (N = 725) n (%) | ||||
| Pain | 6 (0.8) | 11 (1.5) | ||||
| HEPATOBILIARY DISORDERS | ||||||
| Cholelithiasis | 7 (1.0) | 12 (1.7) | ||||
| INFECTIONS AND INFESTATIONS | ||||||
| Nasopharyngitis | 47 (6.4) | 45 (6.2) | ||||
| Urinary tract infection | 37 (5.1) | 32 (4.4) | ||||
| Upper respiratory tract infection | 31 (4.2) | 26 (3.6) | ||||
| Bronchitis | 30 (4.1) | 21 (2.9) | ||||
| Pneumonia | 29 (4.0) | 25 (3.4) | ||||
| Influenza | 23 (3.1) | 20 (2.8) | ||||
| Sinusitis | 17 (2.3) | 15 (2.1) | ||||
| Herpes zoster | 11 (1.5) | 7 (1.0) | ||||
| Cystitis | 10 (1.4) | 8 (1.1) | ||||
| Diverticulitis | 9 (1.2) | 0 (0.0) | ||||
| Cellulitis | 6 (0.8) | 8 (1.1) | ||||
| Lower respiratory tract infection | 3 (0.4) | 10 (1.4) | ||||
| INJURY, POISONING AND PROCEDURAL COMPLICATIONS | ||||||
| Fall | 22 (3.0) | 27 (3.7) | ||||
| Contusion | 16 (2.2) | 11 (1.5) | ||||
| Rib fracture | 16 (2.2) | 14 (1.9) | ||||
| Procedural pain | 15 (2.1) | 3 (0.4) | ||||
| Skin laceration | 12 (1.6) | 4 (0.6) | ||||
| Muscle strain | 10 (1.4) | 6 (0.8) | ||||
| Radius fracture | 2 (0.3) | 12 (1.7) | ||||
| INVESTIGATIONS | ||||||
| Weight decreased | 10 (1.4) | 10 (1.4) | ||||
| Blood cholesterol increased | 6 (0.8) | 8 (1.1) | ||||
| Cardiac murmur | 4 (0.5) | 11 (1.5) | ||||
| METABOLISM AND NUTRITION DISORDERS | ||||||
| Diabetes mellitus | 14 (1.9) | 18 (2.5) | ||||
| Dehydration | 12 (1.6) | 5 (0.7) | ||||
| Hypercholesterolemia | 12 (1.6) | 9 (1.2) | ||||
| Hypokalemia | 12 (1.6) | 7 (1.0) | ||||
| Hyperlipidemia | 10 (1.4) | 11 (1.5) | ||||
| Gout | 9 (1.2) | 7 (1.0) | ||||
| Anorexia | 7 (1.0) | 8 (1.1) | ||||
| MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS | ||||||
| Arthralgia | 92 (12.6) | 80 (11.0) | ||||
| Back pain | 81 (11.1) | 74 (10.2) | ||||
| Pain in extremity | 66 (9.0) | 51 (7.0) | ||||
| Musculoskeletal pain | 41 (5.6) | 26 (3.6) | ||||
| Osteoarthritis | 31 (4.2) | 23 (3.2) | ||||
| Muscle spasms | 18 (2.5) | 17 (2.3) | ||||
| Table 5. Adverse Events Occurring in ≥ 1% of Men with Bone Loss Associated with ADT for Nonmetastatic Prostate Cancer | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 731) n (%) | Placebo (N = 725) n (%) | |||
| Muscular weakness | 15 (2.1) | 13 (1.8) | |||
| Spinal osteoarthritis | 14 (1.9) | 5 (0.7) | |||
| Bone pain | 13 (1.8) | 18 (2.5) | |||
| Joint swelling | 13 (1.8) | 9 (1.2) | |||
| Myalgia | 13 (1.8) | 10 (1.4) | |||
| Arthritis | 12 (1.6) | 18 (2.5) | |||
| Intervertebral disc degeneration | 12 (1.6) | 16 (2.2) | |||
| Neck pain | 12 (1.6) | 11 (1.5) | |||
| Flank pain | 8 (1.1) | 2 (0.3) | |||
| Musculoskeletal chest pain | 4 (0.5) | 11 (1.5) | |||
| Musculoskeletal stiffness | 3 (0.4) | 8 (1.1) | |||
| NEOPLASMS BENIGN, MALIGNANT AND UNSPECIFIED (INCLUDING CYSTS AND POLYPS) | |||||
| Metastases to bone | 34 (4.7) | 25 (3.4) | |||
| Basal cell carcinoma | 13 (1.8) | 7 (1.0) | |||
| NERVOUS SYSTEM DISORDERS | |||||
| Dizziness | 41 (5.6) | 31 (4.3) | |||
| Headache | 22 (3.0) | 27 (3.7) | |||
| Hypoesthesia | 16 (2.2) | 9 (1.2) | |||
| Syncope | 14 (1.9) | 10 (1.4) | |||
| Cerebrovascular accident | 13 (1.8) | 14 (1.9) | |||
| Transient ischemic attack | 11 (1.5) | 8 (1.1) | |||
| Sciatica | 10 (1.4) | 11 (1.5) | |||
| Dementia | 8 (1.1) | 6 (0.8) | |||
| Amnesia | 7 (1.0) | 8 (1.1) | |||
| PSYCHIATRIC DISORDERS | |||||
| Depression | 35 (4.8) | 28 (3.9) | |||
| Insomnia | 23 (3.1) | 16 (2.2) | |||
| Anxiety | 11 (1.5) | 11 (1.5) | |||
| Confusional state | 9 (1.2) | 1 (0.1) | |||
| RENAL AND URINARY DISORDERS | |||||
| Hematuria | 23 (3.1) | 25 (3.4) | |||
| Urinary retention | 23 (3.1) | 11 (1.5) | |||
| Dysuria | 17 (2.3) | 14 (1.9) | |||
| Nocturia | 17 (2.3) | 17 (2.3) | |||
| Pollakiuria | 16 (2.2) | 24 (3.3) | |||
| Urine flow decreased | 11 (1.5) | 4 (0.6) | |||
| Urinary incontinence | 9 (1.2) | 8 (1.1) | |||
| Micturition urgency | 8 (1.1) | 11 (1.5) | |||
| Renal failure | 8 (1.1) | 9 (1.2) | |||
| Nephrolithiasis | 5 (0.7) | 10 (1.4) | |||
| REPRODUCTIVE SYSTEM AND BREAST DISORDERS | |||||
| Gynecomastia | 13 (1.8) | 16 (2.2) | |||
| Erectile dysfunction | 8 (1.1) | 1 (0.1) | |||
| Table 5. Adverse Events Occurring in ≥ 1% of Men with Bone Loss Associated with ADT for Nonmetastatic Prostate Cancer | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 731) n (%) | Placebo (N = 725) n (%) | |||
| RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS | |||||
| Cough | 33 (4.5) | 27 (3.7) | |||
| Dyspnea | 32 (4.4) | 31 (4.3) | |||
| Chronic obstructive pulmonary disease | 13 (1.8) | 10 (1.4) | |||
| Pleural effusion | 13 (1.8) | 7 (1.0) | |||
| SKIN AND SUBCUTANEOUS TISSUE DISORDERS | |||||
| Rash | 16 (2.2) | 17 (2.3) | |||
| Pruritus | 6 (0.8) | 11 (1.5) | |||
| VASCULAR DISORDERS | |||||
| Hypertension | 57 (7.8) | 51 (7.0) | |||
| Hot flush | 38 (5.2) | 32 (4.4) | |||
| Aortic calcification | 10 (1.4) | 9 (1.2) | |||
| Hypotension | 10 (1.4) | 7 (1.0) | |||
| Aortic aneurysm | 6 (0.8) | 9 (1.2) | |||
N = Number of subjects who received ≥ 1 dose of investigational product
n = Number of subjects reporting ≥ 1 event
Includes only treatment-emergent adverse events
New Malignancies
Over the entire study period (double-blind and safety follow-up), the subject incidence of new primary malignancy adverse events was 7.0% in denosumab-treated patients and 5.5% in placebo-treated patients. In the open-label extension period, the subject incidence of new primary malignancy adverse events was 5.5% in the denosumab/denosumab group and 2.2% in the placebo/denosumab group.
Osteonecrosis of the Jaw
Osteonecrosis of the jaw (ONJ) has been reported in patients treated with denosumab or bisphosphonates, another class of anti-resorptive agents (see 7 WARNINGS AND PRECAUTIONS, Osteonecrosis of the Jaw).
Hypocalcemia
Denosumab administration was associated with decreases in serum calcium. Hypocalcemia was reported in 1 (0.1%) subject in the denosumab group and 0 subjects in the placebo group.
Hypersensitivity
Adverse events potentially associated with hypersensitivity were reported in 37 (5.1%) subjects in the denosumab group and 35 (4.8%) subjects in the placebo group.
Infections
Infections were reported in 257 (35.2%) subjects in the denosumab group and 226 (31.2%) subjects in the placebo group. Serious adverse events of infection were reported for 43 (5.9%)
denosumab subjects and 33 (4.6%) placebo subjects. A difference in the subject incidence of serious adverse events of diverticulitis was observed (5 [0.7%] denosumab vs. 0 placebo).
Cataracts
In denosumab-treated men with nonmetastatic prostate cancer receiving ADT, a greater incidence of cataracts was observed (34 [4.7%] denosumab, 9 [1.2%] placebo). During the 24-month safety follow-up period, cataracts were reported in 1.0% of subjects in the prior denosumab group and 1.8% of subjects in the prior placebo group.
Atypical Femoral Fracture
Atypical femoral fractures have been reported in patients receiving denosumab (see 7 WARNINGS AND PRECAUTIONS, Atypical Femoral Fractures).
Treatment to Increase Bone Mass in Women Receiving Adjuvant AI Therapy for Nonmetastatic Breast Cancer Who Have Low Bone Mass and are at High Risk for Fracture
The safety of denosumab in the treatment of bone loss in women with breast cancer receiving adjuvant AI therapy was assessed in a 2 year, randomized, double-blind, placebo-controlled, multinational study.
During the double-blind phase, a total of 252 postmenopausal women aged 35 to 84 years were enrolled. A total of 120 women were exposed to placebo and 129 women were exposed to denosumab, administered once every 6 months as a single 60 mg subcutaneous dose. All women were instructed to take 1000 mg of calcium and at least 400 IU of vitamin D supplementation per day.
Adverse events reported in ≥ 5% of denosumab-treated patients receiving adjuvant AI therapy for breast cancer, and more frequently than in the placebo-treated patients were (denosumab vs. placebo): pain in extremity (19 [14.7%] vs. 14 [11.7%]), back pain (18 [14.0%] vs. 15 [12.5%]), constipation (15 [11.6%] vs. 11 [9.2%]), cough (13 [10.1%] vs. 5 [4.2%]), headache (11 [8.5%] vs. 9 [7.5%]), myalgia (11 [8.5%] vs. 5 [4.2%]), shoulder pain (11 [8.5%] vs. 4 [3.3%]), rash (10 [7.8%] vs. 6 [5.0%]), upper respiratory tract infection (10 [7.8%] vs. 6 [5.0%]), sinusitis (9 [7.0%] vs. 4 [3.3%]), vulvovaginal dryness (9 [7.0%] vs. 3 [2.5%]), anxiety (8 [6.2%] vs. 6 [5.0%]), edema peripheral (8 [6.2%] vs. 5 [4.2%]), vomiting (8 [6.2%] vs. 6 [5.0%]), dyspnea (7 [5.4%] vs. 5 [4.2%]), hypoesthesia (7 [5.4%] vs. 4 [3.3%]), muscle spasms (7 [5.4%] vs. 6 [5.0%]), musculoskeletal chest pain (7 [5.4%] vs. 6 [5.0%]), and urinary tract infection (7 [5.4%] vs. 5 [4.2%]).
New primary malignancy was reported in 0 patients in the denosumab group and 1 patient in the placebo group (0.8%) (gastric cancer). The incidence of malignant disease progression (breast cancer) was 3% in both treatment groups (4 subjects in the denosumab group, 4 subjects in the placebo group), with 1 death in each treatment group being attributable to underlying breast cancer. During the safety follow-up phase, new primary malignancies were reported in 1 patient in the prior denosumab group (adenocarcinoma of the pancreas) and 1 patient in the prior placebo group (multiple myeloma). Three patients (3.1%) in the prior denosumab group and 4 patients (4.4%) in the prior placebo group had an adverse event of metastasis.
A higher number of positively adjudicated fracture events was observed in patients treated with denosumab after discontinuation of treatment, compared with the 24 months treatment phase (off-treatment vs. on-treatment): osteoporotic vertebral fracture: 2 (2.1%) vs. 0; non-vertebral: 11 (11.5%) vs. 8 (6.0%). In patients treated with placebo, no increase was noted: osteoporotic vertebral fracture: 0 vs. 0; non-vertebral: 5 (5.6%) vs. 8 (6.0%).
The incidence of SAEs was 14.7% (n = 19) in the denosumab group and 9.2% (n = 11) in the placebo group. The 3 most common serious adverse events were osteoarthritis (2 [1.6%] denosumab, 0 [0.0%] placebo), myocardial infarction (1 [0.8%] denosumab, 0 [0.0%] placebo), and transient ischemic attack (1 [0.8%] denosumab, 1 [0.8%] placebo). Deaths occurred in 1 subject (0.8%) in the denosumab group and 1 subject (0.8%) in the placebo group.
The percentage of patients who withdrew from the study due to adverse events was 1 (0.8%) and 5 (4.2%) for the denosumab and placebo groups, respectively.
Adverse events reported in ≥ 1% of denosumab-treated or placebo-treated patients are shown in Table 6.
| Table 6. Adverse Events Occurring in ≥ 1% of Women with Bone Loss Associated with Adjuvant AI Therapy for Breast Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 129) n (%) | Placebo (N = 120) n (%) | ||||
| BLOOD AND LYMPHATIC SYSTEM DISORDERS | ||||||
| Anemia | 2 (1.6) | 3 (2.5) | ||||
| CARDIAC DISORDERS | ||||||
| Palpitations | 2 (1.6) | 2 (1.7) | ||||
| Atrial fibrillation | 0 (0.0) | 2 (1.7) | ||||
| Cardiac failure congestive | 0 (0.0) | 2 (1.7) | ||||
| EAR AND LABYRINTH DISORDERS | ||||||
| Tinnitus | 0 (0.0) | 2 (1.7) | ||||
| ENDOCRINE DISORDERS | ||||||
| Hypothyroidism | 3 (2.3) | 2 (1.7) | ||||
| EYE DISORDERS | ||||||
| Visual disturbance | 3 (2.3) | 0 (0.0) | ||||
| Dry eye | 2 (1.6) | 0 (0.0) | ||||
| Eye hemorrhage | 0 (0.0) | 2 (1.7) | ||||
| GASTROINTESTINAL DISORDERS | ||||||
| Constipation | 15 (11.6) | 11 (9.2) | ||||
| Nausea | 10 (7.8) | 11 (9.2) | ||||
| Vomiting | 8 (6.2) | 6 (5.0) | ||||
| Abdominal pain | 6 (4.7) | 4 (3.3) | ||||
| Diarrhea | 5 (3.9) | 9 (7.5) | ||||
| Dyspepsia | 4 (3.1) | 5 (4.2) | ||||
| Table 6. Adverse Events Occurring in ≥ 1% of Women with Bone Loss Associated with Adjuvant AI Therapy for Breast Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 129) n (%) | Placebo (N = 120) n (%) | ||||
| Dry mouth | 3 (2.3) | 2 (1.7) | ||||
| Hemorrhoids | 3 (2.3) | 2 (1.7) | ||||
| Abdominal discomfort | 2 (1.6) | 2 (1.7) | ||||
| Abdominal pain upper | 2 (1.6) | 1 (0.8) | ||||
| Gastroesophageal reflux disease | 2 (1.6) | 8 (6.7) | ||||
| Stomatitis | 2 (1.6) | 1 (0.8) | ||||
| Abdominal distension | 0 (0.0) | 2 (1.7) | ||||
| Hiatus hernia | 0 (0.0) | 2 (1.7) | ||||
| Irritable bowel syndrome | 0 (0.0) | 2 (1.7) | ||||
| GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS | ||||||
| Fatigue | 17 (13.2) | 17 (14.2) | ||||
| Edema peripheral | 8 (6.2) | 5 (4.2) | ||||
| Chest pain | 6 (4.7) | 2 (1.7) | ||||
| Pain | 5 (3.9) | 3 (2.5) | ||||
| Pyrexia | 4 (3.1) | 1 (0.8) | ||||
| Non-cardiac chest pain | 3 (2.3) | 1 (0.8) | ||||
| Asthenia | 2 (1.6) | 1 (0.8) | ||||
| Axillary pain | 2 (1.6) | 1 (0.8) | ||||
| Injection site pain | 2 (1.6) | 2 (1.7) | ||||
| Localised edema | 2 (1.6) | 0 (0.0) | ||||
| Pelvic mass | 2 (1.6) | 0 (0.0) | ||||
| Malaise | 1 (0.8) | 3 (2.5) | ||||
| HEPATOBILIARY DISORDERS | ||||||
| Cholelithiasis | 1 (0.8) | 4 (3.3) | ||||
| IMMUNE SYSTEM DISORDERS | ||||||
| Hypersensitivity | 3 (2.3) | 3 (2.5) | ||||
| INFECTIONS AND INFESTATIONS | ||||||
| Upper respiratory tract infection | 10 (7.8) | 6 (5.0) | ||||
| Sinusitis | 9 (7.0) | 4 (3.3) | ||||
| Urinary tract infection | 7 (5.4) | 5 (4.2) | ||||
| Bronchitis | 5 (3.9) | 7 (5.8) | ||||
| Herpes zoster | 4 (3.1) | 2 (1.7) | ||||
| Influenza | 4 (3.1) | 5 (4.2) | ||||
| Nasopharyngitis | 4 (3.1) | 4 (3.3) | ||||
| Cellulitis | 3 (2.3) | 1 (0.8) | ||||
| Herpes simplex | 3 (2.3) | 0 (0.0) | ||||
| Hordeolum | 3 (2.3) | 0 (0.0) | ||||
| Pneumonia | 2 (1.6) | 1 (0.8) | ||||
| Tinea infection | 2 (1.6) | 0 (0.0) | ||||
| Vaginal infection | 0 (0.0) | 2 (1.7) | ||||
| INJURY, POISONING AND PROCEDURAL COMPLICATIONS | ||||||
| Procedural pain | 4 (3.1) | 3 (2.5) | ||||
| Contusion | 3 (2.3) | 5 (4.2) | ||||
| Table 6. Adverse Events Occurring in ≥ 1% of Women with Bone Loss Associated with Adjuvant AI Therapy for Breast Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 129) n (%) | Placebo (N = 120) n (%) | ||||
| Foot fracture | 3 (2.3) | 2 (1.7) | ||||
| Excoriation | 2 (1.6) | 0 (0.0) | ||||
| Fibula fracture | 2 (1.6) | 0 (0.0) | ||||
| Joint sprain | 2 (1.6) | 3 (2.5) | ||||
| Post-traumatic pain | 2 (1.6) | 0 (0.0) | ||||
| Rib fracture | 2 (1.6) | 1 (0.8) | ||||
| Fall | 1 (0.8) | 4 (3.3) | ||||
| Meniscus lesion | 1 (0.8) | 2 (1.7) | ||||
| Radius fracture | 1 (0.8) | 2 (1.7) | ||||
| Incision site complication | 0 (0.0) | 3 (2.5) | ||||
| INVESTIGATIONS | ||||||
| Weight decreased | 5 (3.9) | 2 (1.7) | ||||
| Blood cholesterol increased | 4 (3.1) | 1 (0.8) | ||||
| Blood pressure increased | 3 (2.3) | 1 (0.8) | ||||
| Weight increased | 1 (0.8) | 3 (2.5) | ||||
| METABOLISM AND NUTRITION DISORDERS | ||||||
| Decreased appetite | 4 (3.1) | 3 (2.5) | ||||
| Hypercholesterolemia | 3 (2.3) | 1 (0.8) | ||||
| Hypokalemia | 3 (2.3) | 2 (1.7) | ||||
| Anorexia | 2 (1.6) | 1 (0.8) | ||||
| MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS | ||||||
| Arthralgia | 31 (24.0) | 30 (25.0) | ||||
| Pain in extremity | 19 (14.7) | 14 (11.7) | ||||
| Back pain | 18 (14.0) | 15 (12.5) | ||||
| Myalgia | 11 (8.5) | 5 (4.2) | ||||
| Shoulder pain | 11 (8.5) | 4 (3.3) | ||||
| Muscle spasms | 7 (5.4) | 6 (5.0) | ||||
| Musculoskeletal chest pain | 7 (5.4) | 6 (5.0) | ||||
| Osteoarthritis | 6 (4.7) | 3 (2.5) | ||||
| Arthritis | 5 (3.9) | 6 (5.0) | ||||
| Bone pain | 5 (3.9) | 8 (6.7) | ||||
| Exostosis | 4 (3.1) | 1 (0.8) | ||||
| Musculoskeletal discomfort | 4 (3.1) | 1 (0.8) | ||||
| Intervertebral disc protrusion | 3 (2.3) | 2 (1.7) | ||||
| Joint swelling | 3 (2.3) | 3 (2.5) | ||||
| Osteopenia | 3 (2.3) | 0 (0.0) | ||||
| Bunion | 2 (1.6) | 0 (0.0) | ||||
| Joint range of motion decreased | 2 (1.6) | 1 (0.8) | ||||
| Muscular weakness | 2 (1.6) | 0 (0.0) | ||||
| Neck pain | 2 (1.6) | 1 (0.8) | ||||
| Tendonitis | 2 (1.6) | 3 (2.5) | ||||
| Musculoskeletal pain | 0 (0.0) | 2 (1.7) | ||||
| Musculoskeletal stiffness | 0 (0.0) | 2 (1.7) | ||||
| Table 6. Adverse Events Occurring in ≥ 1% of Women with Bone Loss Associated with Adjuvant AI Therapy for Breast Cancer | ||||||
|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 129) n (%) | Placebo (N = 120) n (%) | ||||
| NEOPLASMS BENIGN, MALIGNANT AND UNSPECIFIED (INCLUDING CYSTS AND POLYPS) | ||||||
| Benign breast neoplasm | 5 (3.9) | 1 (0.8) | ||||
| Basal cell carcinoma | 2 (1.6) | 3 (2.5) | ||||
| Breast cancer in situ | 2 (1.6) | 0 (0.0) | ||||
| Metastases to bone | 2 (1.6) | 3 (2.5) | ||||
| Seborrheic keratosis | 2 (1.6) | 0 (0.0) | ||||
| Uterine leiomyoma | 2 (1.6) | 0 (0.0) | ||||
| NERVOUS SYSTEM DISORDERS | ||||||
| Headache | 11 (8.5) | 9 (7.5) | ||||
| Hypoesthesia | 7 (5.4) | 4 (3.3) | ||||
| Dizziness | 5 (3.9) | 4 (3.3) | ||||
| Neuropathy | 3 (2.3) | 0 (0.0) | ||||
| Tremor | 3 (2.3) | 0 (0.0) | ||||
| Amnesia | 2 (1.6) | 0 (0.0) | ||||
| Memory impairment | 2 (1.6) | 0 (0.0) | ||||
| Neuropathy peripheral | 2 (1.6) | 1 (0.8) | ||||
| Paresthesia | 2 (1.6) | 2 (1.7) | ||||
| Neuralgia | 0 (0.0) | 2 (1.7) | ||||
| PSYCHIATRIC DISORDERS | ||||||
| Insomnia | 12 (9.3) | 14 (11.7) | ||||
| Anxiety | 8 (6.2) | 6 (5.0) | ||||
| Depression | 7 (5.4) | 11 (9.2) | ||||
| Mood swings | 3 (2.3) | 0 (0.0) | ||||
| RENAL AND URINARY DISORDERS | ||||||
| Pollakiuria | 5 (3.9) | 1 (0.8) | ||||
| Incontinence | 3 (2.3) | 0 (0.0) | ||||
| Nocturia | 2 (1.6) | 1 (0.8) | ||||
| REPRODUCTIVE SYSTEM AND BREAST DISORDERS | ||||||
| Vulvovaginal dryness | 9 (7.0) | 3 (2.5) | ||||
| Breast cyst | 3 (2.3) | 0 (0.0) | ||||
| Breast pain | 3 (2.3) | 6 (5.0) | ||||
| Vaginal hemorrhage | 3 (2.3) | 1 (0.8) | ||||
| Breast tenderness | 2 (1.6) | 1 (0.8) | ||||
| Breast induration | 0 (0.0) | 2 (1.7) | ||||
| RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS | ||||||
| Cough | 13 (10.1) | 5 (4.2) | ||||
| Dyspnea | 7 (5.4) | 5 (4.2) | ||||
| Pharyngolaryngeal pain | 5 (3.9) | 1 (0.8) | ||||
| Nasal congestion | 3 (2.3) | 0 (0.0) | ||||
| Respiratory tract congestion | 2 (1.6) | 1 (0.8) | ||||
| Rhinorrhea | 2 (1.6) | 0 (0.0) | ||||
| Rhinitis allergic | 1 (0.8) | 2 (1.7) | ||||
| Sinus congestion | 1 (0.8) | 2 (1.7) | ||||
| Table 6. Adverse Events Occurring in ≥ 1% of Women with Bone Loss Associated with Adjuvant AI Therapy for Breast Cancer | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Preferred Term | Denosumab (N = 129) n (%) | Placebo (N = 120) n (%) | |||
| Chronic obstructive pulmonary disease | 0 (0.0) | 2 (1.7) | |||
| Epistaxis | 0 (0.0) | 2 (1.7) | |||
| Pneumonitis | 0 (0.0) | 2 (1.7) | |||
| SKIN AND SUBCUTANEOUS TISSUE DISORDERS | |||||
| Rash | 10 (7.8) | 6 (5.0) | |||
| Alopecia | 5 (3.9) | 2 (1.7) | |||
| Night sweats | 3 (2.3) | 0 (0.0) | |||
| Dry skin | 2 (1.6) | 1 (0.8) | |||
| Erythema | 2 (1.6) | 2 (1.7) | |||
| Skin lesion | 2 (1.6) | 1 (0.8) | |||
| Dermatitis | 1 (0.8) | 2 (1.7) | |||
| Hyperhidrosis | 1 (0.8) | 2 (1.7) | |||
| Dermatitis contact | 0 (0.0) | 2 (1.7) | |||
| Nail disorder | 0 (0.0) | 3 (2.5) | |||
| VASCULAR DISORDERS | |||||
| Hot flush | 7 (5.4) | 8 (6.7) | |||
| Lymphoedema | 4 (3.1) | 4 (3.3) | |||
| Hypertension | 2 (1.6) | 7 (5.8) | |||
N = Number of subjects who received ≥ 1 dose of investigational product
n = Number of subjects reporting ≥ 1 event
Includes only treatment-emergent adverse events
Treatment and Prevention of Glucocorticoid-Induced Osteoporosis in Women and Men at High Risk for Fracture
The safety of denosumab in the treatment of glucocorticoid-induced osteoporosis was demonstrated in a 1-year, randomized, multicentre, double-blind, double-dummy, parallel-group, active-controlled study of 795 patients (70% women and 30% men) aged 20 to 94 years (mean age of 63.1 years) treated with ≥ 7.5 mg daily oral prednisone (or equivalent) at high risk for fracture.
Two subpopulations were studied: glucocorticoid-continuing (≥ 7.5 mg daily prednisone or its equivalent for ≥ 3 months prior to study enrollment and planning to continue treatment for a total of at least 6 months; n = 505) and glucocorticoid-initiating (≥ 7.5 mg daily prednisone or its equivalent for < 3 months prior to study enrollment and planning to continue treatment for a total of at least 6 months; n = 290).
A total of 394 patients were exposed to denosumab, administered once every 6 months as a single 60 mg subcutaneous injection. A total of 384 patients were exposed to risedronate, administered orally at a dose of 5 mg once daily (active control). All patients were instructed to take at least 1000 mg calcium and 800 IU vitamin D supplementation daily.
The most common adverse events reported with denosumab were musculoskeletal pain (denosumab 54 [13.7%] versus risedronate 56 [14.6%]), upper respiratory tract infections
(denosumab 45 [11.4%] versus risedronate 48 [12.5%]) and urinary tract infections (denosumab 21 [5.3%] versus risedronate 20 [5.2%]).
Sixty-three (63) serious adverse events (SAEs) were reported in the denosumab group (16.0%) and 65 reported in the risedronate group (16.9%). The most frequent SAEs reported in ≥ 0.5% of patients in the denosumab group were pneumonia (1.3%, n = 5), cardiac failure (0.8%, n = 3), and transient ischemic attack (0.8%, n = 3). In the risedronate group, the most frequent SAEs reported were pneumonia (1.6%, n = 6), osteoarthritis (1.0%, n = 4), pulmonary embolism (1.0%, n = 4), and back pain (0.8%, n = 3). Eight (8) deaths were reported: 6 patients (1.5%) in the denosumab group and 2 patients (0.5%) in the risedronate group. In the denosumab group, the fatal adverse events (1 patient each) were alveolitis allergic, cardiopulmonary failure, cerebral ischemia, cerebrovascular accident, neoplasm, and organizing pneumonia.
The percentage of patients who withdrew from the study due to adverse events was 3.8% (n = 15) in the denosumab group and 3.6% (n = 14) in the risedronate group.
Adverse events reported in ≥ 1% of denosumab-treated or risedronate-treated patients by system organ class and medical concept groups / preferred term are shown in Table 7.
| Table 7. Adverse Events Occurring in ≥ 1% of Patients with Glucocorticoid-Induced Osteoporosis at High Risk for Fracture | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Medical Concept Groupa /Preferred Termb | Denosumab 60 mg Q6M (N = 394) n (%) | Risedronate 5 mg QD (N = 384) n (%) | |||
| BLOOD AND LYMPHATIC SYSTEM DISORDERS | |||||
| Anemia1a | 15 (3.8) | 15 (3.9) | |||
| CARDIAC DISORDERS | |||||
| Cardiac arrhythmias2 | 7 (1.8) | 6 (1.6) | |||
| Coronary artery disorders3 | 4 (1.0) | 5 (1.3) | |||
| Cardiac failure4 | 4 (1.0) | 2 (0.5) | |||
| EAR AND LABYRINTH DISORDERS | |||||
| Vertigo | 4 (1.0) | 4 (1.0) | |||
| EYE DISORDERS | |||||
| Cataract | 5 (1.3) | 15 (3.9) | |||
| Glaucoma5 | 2 (0.5) | 4 (1.0) | |||
| GASTROINTESTINAL DISORDERS | |||||
| Abdominal pain6 | 20 (5.1) | 13 (3.4) | |||
| Dyspepsia | 12 (3.0) | 10 (2.6) | |||
| Diarrhea | 11 (2.8) | 13 (3.4) | |||
| Constipation | 11 (2.8) | 6 (1.6) | |||
| Vomiting | 10 (2.5) | 6 (1.6) | |||
| Nausea | 9 (2.3) | 14 (3.6) | |||
| Gastritis7 | 4 (1.0) | 5 (1.3) | |||
| Hemorrhoids8 | 4 (1.0) | 3 (0.8) | |||
| Abdominal distension | 4 (1.0) | 1 (0.3) | |||
| Hernias9 | 3 (0.8) | 4 (1.0) | |||
| Table 7. Adverse Events Occurring in ≥ 1% of Patients with Glucocorticoid-Induced Osteoporosis at High Risk for Fracture | |||||||
|---|---|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Medical Concept Groupa /Preferred Termb | Denosumab 60 mg Q6M (N = 394) n (%) | Risedronate 5 mg QD (N = 384) n (%) | |||||
| Gastrooesophageal reflux disease | 2 (0.5) | 6 (1.6) | |||||
| Colitis10 | 0 (0.0) | 4 (1.0) | |||||
| GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS | |||||||
| Fatigue | 6 (1.5) | 5 (1.3) | |||||
| Asthenia | 6 (1.5) | 2 (0.5) | |||||
| Pyrexia | 4 (1.0) | 4 (1.0) | |||||
| Edema peripheral | 4 (1.0) | 2 (0.5) | |||||
| Peripheral swelling | 2 (0.5) | 4 (1.0) | |||||
| INFECTIONS AND INFESTATIONS | |||||||
| Upper respiratory tract infections11 | 45 (11.4) | 48 (12.5) | |||||
| Urinary tract infections12a | 21 (5.3) | 20 (5.2) | |||||
| Bronchitis13 | 16 (4.1) | 12 (3.1) | |||||
| Gastrointestinal infections14 | 15 (3.8) | 10 (2.6) | |||||
| Oral infections15 | 9 (2.3) | 7 (1.8) | |||||
| Pneumonia16 | 8 (2.0) | 9 (2.3) | |||||
| Respiratory tract infection | 6 (1.5) | 5 (1.3) | |||||
| Herpes infection17 | 2 (0.5) | 7 (1.8) | |||||
| INJURY, POISONING AND PROCEDURAL COMPLICATIONS | |||||||
| Non-vertebral fractures18 | 20 (5.1) | 14 (3.6) | |||||
| Vertebral fracture19 | 8 (2.0) | 9 (2.3) | |||||
| Fall | 8 (2.0) | 7 (1.8) | |||||
| Procedural pain | 1 (0.3) | 4 (1.0) | |||||
| INVESTIGATIONS | |||||||
| Weight decreased | 1 (0.3) | 4 (1.0) | |||||
| METABOLISM AND NUTRITION DISORDERS | |||||||
| Diabetes mellitus20 | 8 (2.0) | 3 (0.8) | |||||
| Hyperglycemia | 4 (1.0) | 6 (1.6) | |||||
| Hypercholesterolemia21a | 2 (0.5) | 5 (1.3) | |||||
| MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS | |||||||
| Musculoskeletal pain22a | 54 (13.7) | 56 (14.6) | |||||
| Osteoarthritis | 8 (2.0) | 13 (3.4) | |||||
| Polymyalgia rheumatica | 8 (2.0) | 1 (0.3) | |||||
| Rheumatoid arthritis | 5 (1.3) | 10 (2.6) | |||||
| Muscle spasms | 5 (1.3) | 3 (0.8) | |||||
| NERVOUS SYSTEM DISORDERS | |||||||
| Headaches23 | 15 (3.8) | 10 (2.6) | |||||
| Dizziness | 9 (2.3) | 8 (2.1) | |||||
| Paresthesia | 4 (1.0) | 3 (0.8) | |||||
| PSYCHIATRIC DISORDERS | |||||||
| Insomnia | 3 (0.8) | 5 (1.3) | |||||
| RENAL AND URINARY DISORDERS | |||||||
| Renal impairment/ failure24 | 3 (0.8) | 10 (2.6) | |||||
| Table 7. Adverse Events Occurring in ≥ 1% of Patients with Glucocorticoid-Induced Osteoporosis at High Risk for Fracture | |||||
|---|---|---|---|---|---|
SYSTEM ORGAN CLASS Medical Concept Groupa /Preferred Termb | Denosumab 60 mg Q6M (N = 394) n (%) | Risedronate 5 mg QD (N = 384) n (%) | |||
| RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS | |||||
| Cough | 6 (1.5) | 7 (1.8) | |||
| Dyspnea | 5 (1.3) | 6 (1.6) | |||
| Epistaxis | 4 (1.0) | 0 (0.0) | |||
| Asthma | 1 (0.3) | 8 (2.1) | |||
| Pulmonary embolism | 0 (0.0) | 4 (1.0) | |||
| SKIN AND SUBCUTANEOUS TISSUE DISORDERS | |||||
| Rash25 | 4 (1.0) | 4 (1.0) | |||
| Dermatitis and eczema26 | 4 (1.0) | 1 (0.3) | |||
| Alopecia | 3 (0.8) | 5 (1.3) | |||
| SURGICAL AND MEDICAL PROCEDURES | |||||
| Tooth extraction | 1 (0.3) | 6 (1.6) | |||
| VASCULAR DISORDERS | |||||
| Hypertension27 | 16 (4.1) | 13 (3.4) | |||
N = Number of subjects who received ≥ 1 dose of investigational product
Q6M = Every 6 months; QD = Every day
The cut-off of ≥ 1% applies to the subject incidence rate of medical concept groups or preferred terms.
a Medical concept group is placed in the most clinically relevant system organ class (SOC) but contains preferred terms from more than one SOC.
b Preferred terms are listed within medical concept groups in order of frequency reported with respect to denosumab.
Medical concept groups were identified as following:
1Anemia, Iron deficiency anemia, Hypochromic anemia, Microcytic anemia, Hemoglobin decreased
2Atrial fibrillation, Tachycardia, Supraventricular extrasystoles, Supraventricular tachycardia, Ventricular tachycardia, Arrhythmia, Cardio-respiratory arrest, Defect conduction intraventricular
3Angina pectoris, Coronary artery disease, Myocardial ischemia, Acute myocardial infarction, Myocardial infarction
4Cardiac failure, Cardiac failure congestive
5Glaucoma, Angle closure glaucoma
6Abdominal pain upper, Abdominal pain, Abdominal pain lower, Gastrointestinal pain
7Gastritis, Chronic gastritis, Gastritis erosive, Reflux gastritis
8Hemorrhoids, Hemorrhoidal hemorrhage
9Hiatus hernia, Inguinal hernia, Inguinal hernia strangulated
10Colitis, Colitis ulcerative
11Nasopharyngitis, Upper respiratory tract infection, Influenza, Sinusitis, Pharyngitis, Tonsillitis, Rhinitis, Viral pharyngitis, Viral upper respiratory tract infection, Acute sinusitis, Laryngitis, Peritonsillar abscess, Sinusitis bacterial
12Urinary tract infection, Cystitis, Urinary tract infection bacterial, Pyelonephritis, Pyelonephritis acute, Cystitis Escherichia, Urogenital infection bacterial, Cystitis interstitial, Urinary tract infection viral
13Bronchitis, Bronchitis viral, Bronchitis bacterial
14Gastroenteritis, Diverticulitis, Gastroenteritis viral, Helicobacter gastritis, Gastrointestinal infection, Abdominal abscess, Clostridium colitis, Clostridium difficile colitis
15Gingivitis, Tooth infection, Periodontitis, Pulpitis dental, Oral candidiasis, Oral infection, Tooth abscess
16Pneumonia, Pneumonia bacterial
17Genital herpes simplex, Herpes simplex, Herpes zoster, Herpes virus infection, Herpes zoster cutaneous disseminated
18Rib fracture, Foot fracture, Humerus fracture, Pubis fracture, Femur fracture, Hand fracture, Radius fracture, Acetabulum fracture, Fibula fracture, Skull fracture, Femoral neck fracture, Patella fracture
19Thoracic vertebral fracture, Lumbar vertebral fracture, Fractured sacrum
20Diabetes mellitus, Type 2 diabetes mellitus
21Hypercholesterolemia, Blood cholesterol increased
22Back pain, Arthralgia, Pain in extremity, Bone pain, Myalgia, Musculoskeletal pain, Spinal pain, Neck pain, Musculoskeletal chest pain, Non-cardiac chest pain, Pain in jaw, Fibromyalgia, Flank pain, Limb discomfort, Musculoskeletal discomfort
23Headache, Migraine, Migraine with aura, Sinus headache
24Renal impairment, Renal failure, Acute kidney injury, Chronic kidney disease
25Rash, Rash generalised, Rash vesicular
26Seborrhoeic dermatitis, Dermatitis atopic, Eczema, Intertrigo
27Hypertension, Diastolic hypertension
New Malignancies
The subject incidence of new primary malignancy adverse events at 12 months was 5 (1.3%) in the denosumab group and 3 (0.8%) in the risedronate group.
Osteonecrosis of the Jaw
No cases of osteonecrosis of the jaw (ONJ) were reported.
Hypocalcemia
Denosumab administration was associated with decreases in serum calcium. Hypocalcemia was reported in 1 (0.3%) patient in the denosumab group and 0 patients in the risedronate group.
Hypersensitivity
Adverse events potentially associated with hypersensitivity were reported in 19 (4.8%) patients in the denosumab group and 12 (3.1%) patients in the risedronate group.
Infections
Infections were reported in 105 (26.6%) patients in the denosumab group and 111 (28.9%) patients in the risedronate group. Serious adverse events of infection were reported for 17 (4.3%) denosumab patients and 15 (3.9%) risedronate patients. The most commonly reported serious infection was pneumonia in both groups (denosumab [1.3%, n = 5]; risedronate [1.6%, n = 6]).
Atypical Femoral Fracture
Atypical femoral fracture (AFF) was reported in 1 (0.3%) patient in the denosumab group and 0 patients in the risedronate group.
Fracture
The subject incidence of clinical fractures was 4.8% (n = 19) in the denosumab group and 3.8% (n = 15) in the risedronate group. The subject incidence of new vertebral fractures was 2.7% (n = 9) in the denosumab group and 3.2% (n = 11) in the risedronate group.
8.3 Less Common Clinical Trial Adverse Reactions
Postmenopausal Osteoporosis*
MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS: Arthralgia, Muscle spasms, Pain in extremity, Bone pain, Myalgia, Musculoskeletal stiffness, Musculoskeletal pain, Osteoarthritis, Neck pain, Exostosis, Joint swelling, Muscle fatigue, Limb discomfort, Tendonitis, Joint stiffness, Muscular weakness, Nodule on extremity, Fistula, Groin pain, Joint ankylosis, Limb deformity, Muscle hemorrhage, Rheumatoid arthritis, Spinal deformity, Spondylitis, Polymyalgia rheumatica, Sensation of heaviness, Arthritis, Bone callus excessive, Foot deformity, Muscle atrophy, Osteitis, Renal rickets, Resorption bone increased, Synovitis, Tendon pain, Tenosynovitis
GASTROINTESTINAL DISORDERS: Nausea, Constipation, Diarrhea, Vomiting, Abdominal pain, Flatulence, Abdominal pain upper, Dry mouth, Gastritis, Dyspepsia, Stomach discomfort, Abdominal distension, Abdominal discomfort, Abdominal pain lower, Celiac disease, Fecalith, Frequent bowel movements, Gastric ulcer, Gastritis erosive, Gastroesophageal reflux disease, Gingivitis, Glossodynia, Hemorrhoids, Irritable bowel syndrome, Oral cavity fistula, Pancreatitis, Pancreatitis acute, Rectal hemorrhage, Aphthous stomatitis, Change of bowel habit, Enterocolitis, Gastroduodenitis, Gastrointestinal hemorrhage, Lip swelling, Melena, Esophageal spasm, Rectal prolapse, Reflux Esophagitis, Tongue ulceration
INFECTIONS AND INFESTATIONS: Nasopharyngitis, Respiratory tract infection, Upper respiratory tract infection, Influenza, Urinary tract infection, Rhinitis, Lower respiratory tract infection, Pneumonia, Bronchitis, Cystitis, Sinusitis, Herpes zoster, Oral herpes, Pharyngitis, Herpes virus infection, Tinea pedis, Viral infection, Chlamydial infection, Eczema infected, Gastroenteritis viral, Herpes ophthalmic, Laryngitis, Liver abscess, Lung infection, Viremia, Borrelia infection, Chronic sinusitis, Diverticulitis, Furuncle, Genital infection fungal, Gingival infection, Hematoma infection, Helicobacter infection, Herpes simplex, Sialoadenitis, Tracheitis
NERVOUS SYSTEM DISORDERS: Headache, Dizziness, Paresthesia, Lethargy, Somnolence, Hypoesthesia, Ischemic stroke, Dysgeusia, Sciatica, Tremor, Parosmia, Syncope, Transient ischemic attack, Disturbance in attention, Epilepsy, Freezing phenomenon, Global amnesia, Guillain-Barre syndrome, Head discomfort, Hemicephalalgia, Hypotonia, Poor quality sleep,
Trigeminal neuralgia, Hypersomnia, Loss of consciousness, Memory impairment, Ageusia, Amnesia, Anosmia, Dyskinesia, Formication, Intercostal neuralgia, Migraine, Muscle contractions involuntary, Neuritis cranial, Parkinson's disease, Parkinsonism, Restless legs syndrome
GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS: Asthenia, Fatigue, Injection site pain, Edema peripheral, Injection site erythema, Pain, Influenza like illness, Injection site irritation, Feeling hot, Malaise, Injection site bruising, Injection site reaction, Injection site hematoma, Injection site rash, Pyrexia, Noncardiac chest pain, Peripheral coldness, Chills, Injection site warmth, Chest discomfort, Feeling cold, Gait disturbance, Hernia, Impaired healing, Injection site discomfort, Injection site mass, Injection site swelling, Irritability, Injection site pruritus, Fat tissue increased, Injection site scab, Thirst
SKIN AND SUBCUTANEOUS TISSUE DISORDERS: Pruritus, Rash, Alopecia, Hyperhidrosis, Eczema, Dermatitis allergic, Erythema, Dry skin, Rash macular, Rash pruritic, Onychomadesis, Ecchymosis, Pruritus generalised, Dermatitis, Rosacea, Subcutaneous nodule, Blister, Dermatitis atopic, Hair growth abnormal, Heat rash, Hyperkeratosis, Lichen planus, Nail disorder, Psoriasis, Rash generalised, Skin exfoliation, Skin warm, Urticaria, Acne, Night sweats, Pigmentation disorder, Purpura, Rash maculo-papular, Skin lesion, Skin nodule, Skin wrinkling, Swelling face, Vasculitic rash
VASCULAR DISORDERS: Hypertension, Hot flush, Aortic calcification, Deep vein thrombosis, Flushing, Hematoma, Varicose vein, Arteriosclerosis, Aortic stenosis, Orthostatic hypotension, Peripheral ischemia, Vasculitis, Hypotension, Thrombophlebitis, Hypertensive crisis, Venous thrombosis
RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS: Cough, Pharyngolaryngeal pain, Dyspnea, Dysphonia, Nasal congestion, Epistaxis, Rhinorrhea, Pulmonary embolism, Asthma, Dyspnea exertional, Nocturnal dyspnea, Sinus congestion, Sneezing, Vasomotor rhinitis, Acute pulmonary edema, Nasal dryness, Pleurisy, Productive cough, Rhinitis allergic
CARDIAC DISORDERS: Palpitations, Angina pectoris, Cardiac failure, Arrhythmia, Acute myocardial infarction, Extrasystoles, Ventricular extrasystoles, Atrial fibrillation, Myocardial infarction, Cardiac failure chronic, Coronary artery disease, Hypertensive cardiomyopathy, Ischemic cardiomyopathy, Supraventricular extrasystoles, Tachycardia, Mitral valve incompetence, Tachyarrhythmia
EYE DISORDERS: Cataract, Glaucoma, Conjunctivitis allergic, Dry eye, Ocular discomfort, Eyelid pain, Lacrimation increased, Visual disturbance, Vitreous disorder, Conjunctivitis, Eye pain, Arteriosclerotic retinopathy, Blepharitis, Blepharospasm, Eyelids pruritus, Lacrimal gland enlargement, Photophobia, Vision blurred, Vitreous hemorrhage
EAR AND LABYRINTH DISORDERS: Vertigo, Ear pain, Ear discomfort, Tinnitus, Cerumen impaction, Ear congestion, Ear disorder, Otosalpingitis, Tympanic membrane perforation
NEOPLASMS BENIGN, MALIGNANT AND UNSPECIFIED (INCL CYSTS AND POLYPS): Breast cancer, Ovarian cancer, Basal cell carcinoma, Benign neoplasm of thyroid gland, Benign soft tissue neoplasm, Cerebellar tumour, Cervix carcinoma, Lipoma, Multiple myeloma, Uterine leiomyoma, Benign breast neoplasm, Acral lentiginous melanoma stage unspecified, Adenocarcinoma, Benign bone neoplasm, Benign neoplasm, Bladder neoplasm, Colon cancer, Diffuse large B-cell lymphoma recurrent, Hemangioma, Hemangioma of liver, Lipoma of breast, Melanocytic nevus
BLOOD AND LYMPHATIC SYSTEM DISORDERS: Eosinophilia, Leukopenia, Thrombocytopenia, Anemia, Leukocytosis, Lymphadenopathy, Lymphocytosis, Neutrophilia, Pancytopenia, Neutropenia, Bone marrow failure, Lymphopenia
INVESTIGATIONS: Weight decreased, Blood pressure increased, Alanine aminotransferase increased, Coagulation time shortened, Red blood cell sedimentation rate increased, Blood chloride decreased, Blood sodium decreased, Weight increased, Cardiac murmur, Aspartate aminotransferase increased, Hemoglobin decreased, International normalised ratio increased, Platelet count decreased, Red blood cell count decreased, Rheumatoid factor positive
METABOLISM AND NUTRITION DISORDERS: Hypercalcemia, Anorexia, Hypercholesterolemia, Decreased appetite, Diabetes mellitus, Glucose tolerance impaired, Hypomagnesemia
PSYCHIATRIC DISORDERS: Depression, Depressed mood, Insomnia, Apathy, Dysthymic disorder, Sleep disorder, Restlessness
RENAL AND URINARY DISORDERS: Dysuria, Hematuria, Nephrolithiasis, Acute prerenal failure, Polyuria, Urge incontinence, Urine abnormality, Pollakiuria, Nephrosclerosis, Nocturia, Proteinuria, Renal impairment, Urine odour abnormal
REPRODUCTIVE SYSTEM AND BREAST DISORDERS: Breast pain, Vulvovaginal pruritus, Breast disorder, Vaginal hemorrhage, Breast discomfort, Vulvovaginal dryness, Breast mass, Fibrocystic breast disease, Breast necrosis, Breast tenderness, Vulvovaginal burning sensation
ENDOCRINE DISORDERS: Goitre, Hyperthyroidism, Hypothyroidism, Hyperparathyroidism
INJURY, POISONING AND PROCEDURAL COMPLICATIONS: Thoracic vertebral fracture, Clavicle fracture, Femoral neck fracture, Post procedural hemorrhage, Lumbar vertebral fracture, Fall, Anastomotic ulcer hemorrhage, Contusion, Humerus fracture, Ilium fracture, Joint dislocation, Joint sprain, Post concussion syndrome, Radius fracture, Scratch
HEPATOBILIARY DISORDERS: Liver disorder, Hepatic cyst, Cholecystitis, Cholelithiasis
IMMUNE SYSTEM DISORDERS: Hypersensitivity, Drug hypersensitivity
CONGENITAL, FAMILIAL AND GENETIC DISORDERS: Familial tremor
SURGICAL AND MEDICAL PROCEDURES: Fistula repair
*Terms designated by investigators as related to study drugs
Glucocorticoid-Induced Osteoporosis*
BLOOD AND LYMPHATIC SYSTEM DISORDERS: Leukopenia, Immune thrombocytopenic purpura, Thrombocytopenia
CARDIAC DISORDERS: Mitral valve incompetence, Tricuspid valve incompetence, Palpitations
ENDOCRINE DISORDERS: Hypothyroidism
EYE DISORDERS: Visual acuity reduced
GASTROINTESTINAL DISORDERS: Abdominal discomfort, Gastrointestinal disorder, Flatulence
GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS: Chest pain, Influenza like illness, Malaise
HEPATOBILIARY DISORDERS: Liver disorder
INFECTIONS AND INFESTATIONS: Erysipelas, Onychomycosis
INJURY, POISONING AND PROCEDURAL COMPLICATIONS: Contusion, Meniscus injury, Joint injury, Tooth avulsion
INVESTIGATIONS: Alanine aminotransferase increased, Weight increased, Aspartate aminotransferase increased, Blood glucose increased
METABOLISM AND NUTRITION DISORDERS: Dyslipidemia, Decreased appetite, Dehydration, Hypokalemia
MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS: Bursitis, Arthritis, Muscular weakness, Synovial cyst, Synovitis, Joint swelling, Vertebral foraminal stenosis
NERVOUS SYSTEM DISORDERS: Transient ischemic attack, Sciatica, Carpal tunnel syndrome, Cerebrovascular accident, Tremor
RENAL AND URINARY DISORDERS: Urinary incontinence
REPRODUCTIVE SYSTEM AND BREAST DISORDERS: Ovarian cyst, Benign prostatic hyperplasia
RESPIRATORY, THORACIC AND MEDIASTINAL DISORDERS: Chronic obstructive pulmonary disease, Dyspnea exertional, Sinus congestion
SKIN AND SUBCUTANEOUS TISSUE DISORDERS: Pruritus generalized, Swelling face, Acne, Erythema, Rosacea, Skin disorder
SURGICAL AND MEDICAL PROCEDURES: Knee arthroplasty
VASCULAR DISORDERS: Hematoma, Hot flush
*reported by < 1% and ≥ 0.5% (n = 2) of denosumab-treated patients
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Not applicable
8.5 Postmarket Adverse Reactions
Hypersensitivity Reactions
Hypersensitivity reactions including rash, urticaria, facial swelling, erythema, and anaphylactic reactions have been reported in patients receiving denosumab.
Hypersensitivity Vasculitis
Hypersensitivity vasculitis has been reported in patients receiving denosumab.
Drug Reaction with Eosinophilia and Systemic Symptoms
Drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome has been reported in patients receiving denosumab.
Lichenoid Drug Eruptions
In the postmarketing experience, lichenoid drug eruptions (eg, lichen planus-like reactions) have been observed.
Severe Hypocalcemia
Symptoms of hypocalcemia in denosumab clinical studies include paresthesias or muscle stiffness, twitching, spasms and muscle cramps. In the postmarket setting, severe symptomatic hypocalcemia has been reported in those receiving denosumab and who are at increased risk of hypocalemia, particularly in patients with severe renal impairment, receiving dialysis or treatment with other calcium lowering drugs. In some cases this has resulted in hospitalization, life-threatening events, and fatal cases. Most cases of hypocalcemia occur within the first few weeks of initiating therapy. Symptoms of severe hypocalcemia may include QT interval prolongation, tetany and convulsions and altered mental status. Healthcare Professionals should follow standard medical care guidelines for the treatment of signs and symptoms associated with severe hypocalcemia.See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia for further information on monitoring hypocalcemia.
Musculoskeletal Pain
Musculoskeletal pain, including severe cases, has been reported in patients receiving denosumab.
Osteonecrosis of the Jaw (ONJ)
Osteonecrosis of the jaw has been reported in patients receiving denosumab.
Alopecia
In the postmarketing experience, alopecia has been observed.
9 DRUG INTERACTIONS
9.2 Drug interactions Overview
In subjects with postmenopausal osteoporosis, denosumab (60 mg SC) did not affect the pharmacokinetics of midazolam, which is metabolized by cytochrome P450 3A4 (CYP3A4), indicating that denosumab is not expected to affect the pharmacokinetics of drugs metabolized by this enzyme in this population (see 10 CLINICAL PHARMACOLOGY, Pharmacokinetics).
The pharmacokinetics and pharmacodynamics of denosumab were similar in postmenopausal women with osteoporosis transitioning from alendronate therapy compared to those who had not received prior alendronate therapy.
9.3 Drug-Behavioural Interactions
Interactions with behaviour have not been established.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Jubbonti (denosumab) is a human IgG2 monoclonal antibody with affinity and specificity for human RANK ligand (RANKL). RANKL exists as a transmembrane or soluble protein. RANK ligand is essential for the formation, function and survival of osteoclasts, the sole cell type responsible for bone resorption. Osteoclasts play an important role in bone loss associated with osteoporosis and hormone ablation. Denosumab targets and binds with high affinity and specificity to RANKL, preventing RANKL from activating its only receptor, RANK, on the surface of osteoclasts and their precursors, independent of bone surface. Prevention of RANKL-RANK interaction inhibits osteoclast formation, function and survival, thereby decreasing bone resorption and increasing bone mass and strength in both cortical and trabecular bone throughout the skeleton.
Animal Pharmacology
The single- and multiple-dose pharmacokinetics of denosumab following intravenous or subcutaneous administration of denosumab were evaluated in mice, rats, and cynomolgus monkeys. Serum concentrations of denosumab were determined using a conventional sandwich enzyme-linked immunosorbent assay (ELISA) with a limit of quantification (LOQ) ranging from 0.78 to 5 ng/mL. In addition, tissue distribution (by liquid scintillation counting) and quantitative whole body autoradiography studies were conducted in cynomolgus monkeys following a single SC dose.
In mice and rats, species in which denosumab does not bind RANKL, the intravenous pharmacokinetics of denosumab were linear over the dose range of approximately 0.1 to 10 mg/kg, with low clearance and a volume of distribution at steady-state (Vss) that indicated a lack of extensive extravascular distribution. After a single SC dose (1 mg/kg), maximum serum denosumab concentrations (Cmax) occurred at 72 hours postdose in both species, and bioavailability was 86% in mice and 56% in rats.
Approximately 6- and 15-fold higher clearance was observed in huRANKL and knock-out mice lacking expression of the Fc neonatal receptor (FcRn), respectively, indicating important roles of RANKL and FcRn in denosumab disposition.
In cynomolgus monkeys, a species in which denosumab binds RANKL, the intravenous pharmacokinetics of denosumab were non-linear over the dose range of 0.0016 to 1 mg/kg (with approximately 16-fold higher clearance at the lowest relative to highest dose) but were approximately dose-linear between 1 and 3 mg/kg. At all doses, the Vss indicated a lack of extensive extravascular distribution. The subcutaneous pharmacokinetics of denosumab were also nonlinear in monkeys over the dose range of 0.0016 to 1 mg/kg, but were approximately dose-linear between 1 and 3 mg/kg.
10.2 Pharmacodynamics
In clinical studies, treatment with 60 mg of denosumab resulted in rapid reduction in the bone resorption marker serum type 1 C-telopeptide (CTX) within 6 hours of SC administration by approximately 70%, with reductions of approximately 85% occurring by 3 days. CTX levels were below the limit of assay quantitation (0.049 ng/mL) in 39 to 68% of subjects 1 to 3 months after dosing of denosumab. CTX reductions were maintained over the 6-month dosing interval. At the end of each dosing interval, CTX reductions were partially attenuated from maximal reduction of ≥ 87% to ≥ 45% (range 45% to 80%), as serum denosumab levels diminished, reflecting the reversibility of the effects of denosumab on bone remodelling. These effects were maintained with continued treatment. Consistent with the physiological coupling of bone formation and resorption in skeletal remodeling, subsequent reductions in bone formation markers were observed beginning 1 month after the first dose of denosumab.
Bone turnover markers (bone resorption and formation markers) generally reached pre-treatment levels within 9 months after the last 60 mg SC dose. Upon re-initiation, the degree of inhibition of CTX by denosumab was similar to that observed in patients initiating denosumab treatment.
In a clinical study of postmenopausal women with low bone mass (N = 504) who were previously treated with alendronate for a median duration of 3 years, those transitioning to receive denosumab experienced additional reductions in serum CTX, compared with women who remained on alendronate. In this study, the changes in serum calcium were similar between the 2 groups.
10.3 Pharmacokinetics
In dose ranging studies, denosumab exhibited nonlinear, dose-dependent pharmacokinetics for doses between 0.01 mg/kg to 3.0 mg/kg inclusive. Clearance or apparent clearance (mL/hr/kg) was higher at lower doses and had a linear inverse relationship with dose on a log-log plot. Exposures (SC dosing) based on area under the serum denosumab concentration-time curve (AUC) increased greater than dose-proportionally from 0.01 to 1 mg/kg (700-fold for the 100-fold increase in dose), but approximately dose-proportionally from 1 to 3 mg/kg (3.9-fold for the 3-fold increase in dose) (Figure 1, Table 8 and Table 9).
Figure 1. Individual Serum Denosumab Concentration-Time Profiles Following Single Dose SC Administration at 1.0 mg/kg to Healthy Postmenopausal Women
| Table 8. Mean (SD) Denosumab Pharmacokinetic Parameters Following Single Dose SC Administration of 1.0 mg/kg Denosumab to Healthy Postmenopausal Women (N = 6) | |||||||||
Tmax (days) | Cmax (µg/mL) | AUC0-inf (µg x day/mL) | CL/F (mL/hr) | MRT (days) | t1/2 (days) | t1/2, z (days) | |||
17.5 (7 - 42) | 8.99 (3.34) | 538 (224) | 6.61 (2.93) | 44.2 (6.96) | 30.2 (7.04) | 8.00 (0.975) | |||
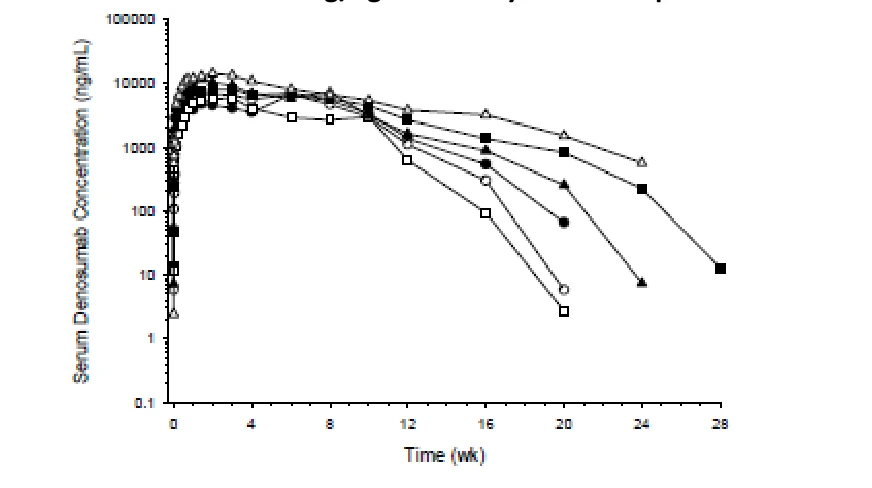
SD = standard deviation; Cmax = Maximum observed concentration; Tmax = time of Cmax (range reported instead of SD); AUC0-inf = Area under the serum concentration-time curve f rom pre-dose to inf inity; CL/F = apparent clearance; MRT = mean residence time; t1/2 = half -life following Cmax; t1/2, z = terminal-phase half -life
| Table 9. Mean (SD) Denosumab Pharmacokinetic Parameters Following SC Administration of 60 mg Denosumab Every 6 Months to Postmenopausal Women with Low BMD (n = 32-46)* | ||||||||||||
| Dose | Tmax (days) | Cmax (µg/mL) | AUC0-tau (µg x day/mL) | CL/F (mL/hr) | MRT (days) | t1/2 (days) | Cmin (µg/mL) | |||||
| 1st | 26 (2.9 - 32) | 7.93 (2.95) | 503 (239) | 6.71 (5.00) | 44.2 (9.48) | 25.4 (8.47) | 0.137 (0.334) | |||||
| 2nd | 29 (1.9 - 42) | 6.94 (3.18) | 448 (239) | 7.50 (5.04) | 45.0 (9.99) | 27.1 (8.99) | 0.132 (0.334) | |||||
SD = standard deviation; Cmax = Maximum observed concentration; Tmax = time of Cmax (range reported instead of SD); AUC0-tau = area under the serum denosumab concentration-time curve over the dosing interval; CL/F = apparent clearance; MRT = mean residence time; t1/2 = half -life following Cmax; Cmin = trough serum denosumab concentration
*1st dose: n = 46 for Tmax, Cmax, AUC0-tau, CL/F, & MRT; n = 32 for t1/2; n = 38 for Cmin
*2nd dose: n = 44 for Tmax, Cmax, AUC0-tau, CL/F, & MRT; n = 33 for t1/2; n = 39 for Cmin
Denosumab pharmacokinetic parameters were not affected by the formation of binding antibodies to denosumab.
At the level of the administered dose, the pharmacokinetics of denosumab do not appear to be affected by gender, age (28 to 87 years), race, or disease state.
In a study of 17 postmenopausal women with osteoporosis, midazolam (2 mg oral) was administered two weeks after a single dose of denosumab (60 mg SC), which approximates the median time to maximum denosumab concentration (Tmax) of 10 days (range: 3 to 21 days). Denosumab did not affect the pharmacokinetics of midazolam, which is metabolized by cytochrome P450 3A4 (CYP3A4). This indicates that denosumab is not expected to alter the pharmacokinetics of drugs metabolized by CYP3A4 in postmenopausal women with osteoporosis.
Seminal Fluid Pharmacokinetic Study
Serum and seminal fluid concentrations of denosumab were measured in 12 healthy male volunteers (age range: 43-65 years). After a single 60 mg subcutaneous administration of denosumab, Cmax [mean (± SD)] values in the serum and seminal fluid samples were 6170 (± 2070) and 100 (± 81.9) ng/mL, respectively, resulting in maximum denosumab concentrations in seminal fluid that were approximately 0-5% of serum levels. The median (range) Tmax values in serum and seminal fluid were estimated as 8.0 (7.9 to 21) and 21 (8.0 to 49) days, respectively. At the last measurement (approximately 15 weeks post-dose), 5 out of 12 subjects had quantifiable concentrations of denosumab in seminal fluid; the mean (± SD) was 21.1 (± 36.5) ng/mL across all subjects.
Special Populations and Conditions
- Pediatrics
Health Canada has not authorized an indication for pediatric use (see 1 INDICATIONS, Pediatrics).
- Geriatrics
The pharmacokinetics of denosumab were not affected by age.
- Ethnic Origin
The pharmacokinetics of denosumab were not affected by race in post-menopausal women.
- Hepatic Insufficiency
No clinical studies have been conducted to evaluate the effect of hepatic impairment on the pharmacokinetics of denosumab.
- Renal Insufficiency
In a study of 55 patients with varying degrees of renal function, including patients on dialysis, the degree of renal impairment had no effect on the pharmacokinetics of denosumab; thus, dose adjustment for renal impairment is not necessary.
11 STORAGE, STABILITY AND DISPOSAL
Store in a refrigerator between 2°C and 8°C. Do not freeze.
Prior to administration, Jubbonti may be allowed to reach room temperature (up to 25°C) in the original carton. Once removed from the refrigerator, Jubbonti must not be exposed to temperatures above 25°C and must be used within 30 days. If not used within the 30 days, Jubbonti should be discarded.
Keep the prefilled syringe in the original carton until ready to use in order to protect from light.
Do not shake the prefilled syringe at any time.
Do not use Jubbonti beyond the expiry date stamped on the label.
Keep out of sight and reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: denosumab
Molecular mass: 145 kDa (approximate)
Structural formula: Denosumab is a fully human IgG2 monoclonal antibody heterotetramer consisting of 2 heavy chains of the gamma 2 subclass (447 amino acids per chain) and 2 light chains of the kappa subclass (215 amino acids per chain).
Physicochemical
Properties: Jubbonti is a clear, colourless to slightly yellowish or slightly brownish solution.
Product Characteristics:
Denosumab is produced in genetically engineered mammalian (Chinese Hamster Ovary) cells.
14 CLINICAL TRIALS
14.5 Clinical Trials - Reference Biologic Drug
Treatment of Osteoporosis in Postmenopausal Women
In postmenopausal women with osteoporosis, the safety and efficacy of denosumab were assessed in a randomized double-blind controlled study.
| Table 10. Study 1 (FREEDOM) | ||||||
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (range) (yrs) | ||
| Study 1 (FREEDOM) | Phase 3, randomized, double-blind, placebo-controlled | Denosumab 60 mg or placebo SC injection every 6 months for 3 years | 7808 patients with osteoporosis (Denosumab: 3902 Placebo: 3906) | 72 (60, 91) | ||
The efficacy and safety of denosumab administered once every 6 months for 3 years were investigated in postmenopausal women (7,808 women aged 60-91 years, of which 23.6% had prevalent vertebral fractures) with baseline bone mineral density (BMD) T-scores at the lumbar spine or total hip between –2.5 and –4.0 and a mean absolute 10-year fracture probability of 18.60% (deciles: 7.9-32.4%) for major osteoporotic fracture and 7.22% (deciles: 1.4-14.9%) for hip fracture (Table 10 ) . Women with other diseases or on therapies that may affect bone (such as rheumatoid arthritis, osteogenesis imperfecta, and Paget’s disease) were excluded from this study. Women were randomized to receive SC injections of either placebo (n = 3906) or denosumab 60 mg (n = 3902) once every 6 months. Women received calcium (at least 1,000 mg) and vitamin D (at least 400 IU) supplementation daily. The primary efficacy variable was the incidence of new vertebral fractures over 3 years. Secondary efficacy variables included the incidence of non-vertebral fracture and hip fracture, assessed over 3 years. The study was powered to detect a 45% reduction in the incidence of new vertebral fractures, a 40% decrease in the risk of non-vertebral fractures and a 40% decrease in the risk of hip fractures.
Effects on Fracture Incidence
New Vertebral Fractures
Denosumab, when taken with calcium and vitamin D and compared with calcium and vitamin D alone, significantly reduced the incidence of new vertebral fractures over 36 months from 7.2% in the placebo group to 2.3% in the denosumab group (p < 0.0001). The absolute reduction in risk of vertebral fractures was 4.8% and the relative reduction was 68% (Table 11). The number needed to treat (NNT) over the three years to prevent 1 new vertebral fracture was 20.7 (95% CI: 17.3, 25.8).
| Table 11. The Effect of Denosumab on Vertebral Fracture Incidence over 3 Years | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Proportion of Women with Fracture (%) | Absolute Risk Reduction (%) (95% CI) | Relative Risk Reduction (%) (95% CI) | ||||||||
Placebo N = 3691 (%) | Denosumab N = 3702 (%) | |||||||||
| 0 - 1 Year | 2.2 | 0.9 | 1.4 (0.8, 1.9) | 61 (42, 74)* | ||||||
| 0 - 2 Years | 5.0 | 1.4 | 3.5 (2.7, 4.3) | 71 (61,79)* | ||||||
| 0 - 3 Years | 7.2 | 2.3 | 4.8 (3.9, 5.8) | 68 (59, 74)* | ||||||
*p< 0.0001
N = Number of women in the primary efficacy analysis set
In the long-term, open-label extension of Study 1, among 2343 women who received denosumab in Study 1 and continued on therapy (years 4 through 10 of denosumab treatment), 1343 (57.3%) completed 10 years. Denosumab treatment maintained a low incidence of new vertebral fractures in years 4 through 10 (149 [7.0%] women had at least one new vertebral fracture and 43 [2.4%] women had a clinical vertebral fracture by year 7 of the extension study). The yearly incremental incidences of new vertebral fractures remained low (see Table 12).
Among 2207 women who crossed over to denosumab from placebo in Study 1, 1283 (58.1%) completed 10 years, and the incidence of new vertebral fractures was low (145 [7.3%] had at least one new vertebral fracture and 33 [1.9%] had a clinical vertebral fracture by year 7 of the extension study). The yearly incremental incidences of new vertebral fractures remained low (see Table 12).
| Table 12. The Effect of Denosumab on the Yearly Incidence of New Vertebral Fracture in the Extension Study | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Long-term Denosumab Group1 | Cross-over Denosumab Group2 | |||||||||
| Exposure to Denosumab | Proportion of Women with New Vertebral Fractures (%)3 | Exposure to Denosumab | Proportion of Women with New Vertebral Fractures (%)3 | |||||||
| Year 4 | 1.54 (N = 2116) | Year 1 | 0.94 (N = 1991) | |||||||
| Year 5 | Year 2 | |||||||||
| Year 6 | 1.2 (N = 1809) | Year 3 | 1.5 (N = 1695) | |||||||
| Year 7 | 1.44 (N = 1585) | Year 4 | 1.94 (N = 1508) | |||||||
| Year 8 | Year 5 | |||||||||
| Year 9 | 1.34 (N = 1323) | Year 6 | 1.64 (N = 1267) | |||||||
| Year 10 | Year 7 | |||||||||
1 Long-term denosumab group: women who received denosumab in Study 1 and continued on therapy in the extension
2 Cross-over denosumab group: women who received placebo in Study 1 and transitioned to denosumab in the extension
3 Based on crude incidence
4 Annualized yearly subject incidence
Hip Fractures
The incidence of hip fracture was 1.2% for placebo-treated women compared to 0.7% for denosumab-treated women. The observed absolute reduction in the risk of hip fracture at 3 years was 0.3%, with a 95% CI across the zero (-0.1%, 0.7%), and the relative risk reduction was 40% (95% CI: 0.37, 0.97; p = 0.0362).
Among women who received denosumab for 3 years in Study 1 and continued on therapy in the long-term, open-label extension, denosumab treatment maintained a low incidence of hip fractures in years 4 through 10 (22 [1.2%] women had at least one hip fracture). The yearly incremental incidences of hip fractures remained low (0.3%, <0.1%, 0.2%, 0.1%, 0.2%, <0.1%, and 0.4% during 4, 5, 6, 7, 8, 9 and 10 years of exposure to denosumab, respectively).
Women who crossed over to denosumab from placebo in Study 1, had a low incidence of hip fractures by year 7 of the extension study (26 [1.4%] women had at least one hip fracture). The yearly incremental incidences of hip fractures remained low (0.6%, 0.1%, 0.2%, <0.1%, 0.1%, 0.1% and 0.2% during 1, 2, 3, 4, 5, 6 and 7 years of exposure to denosumab, respectively).
Non-vertebral Fractures
The incidence of non-vertebral fracture was 8.0% for placebo-treated women, compared with 6.5% for denosumab-treated women. The observed absolute reduction in risk of non-vertebral fractures over 3 years was 1.5% (0.3, 2.7) and the relative risk reduction was 20% (95% CI: 5, 33%; p = 0.0106).
The incidences of nonvertebral fractures at other locations were as follows: distal femur (3 [< 0.1%] placebo, 0 [0%] denosumab), forearm (120 [3.1%] placebo, 103 [2.6%] denosumab), wrist (107 [2.7%] placebo, 90 [2.3%] denosumab), humerus (45 [1.2%] placebo, 38 [1.0%] denosumab), proximal humerus (41 [1.0%] placebo, 30 [0.8%] denosumab), clavicle/rib (25 [0.6%] placebo, 34 [0.9%] denosumab), proximal tibia (5 [0.1%] placebo, 3 [< 0.1%] denosumab), and pelvic (13 [0.3%] placebo, 10 [0.3%] denosumab).
Among women who received denosumab for 3 years in Study 1 and continued on therapy in the long-term, open-label extension, denosumab treatment maintained a low incidence of nonvertebral fractures in years 4 through 10 (172 [9.3%] women had at least one nonvertebral fracture). The yearly incremental incidences of nonvertebral fractures remained low (1.5%, 1.2%, 1.8%, 1.6%, 0.8%, 1.1% and 1.9% during 4, 5, 6, 7, 8, 9 and 10 years of exposure to denosumab, respectively). The most common sites for nonvertebral fractures during the long-term, open-label extension of Study 1 were wrist (n = 70), rib/clavicle (n = 23), hip (n = 22), and ankle (n = 17) (with n = number of affected women).
Among women who crossed over to denosumab from placebo in Study 1,219 (12.3%) women had at least one nonvertebral fracture by year 7 of the extension study. The yearly incremental incidences of nonvertebral fractures remained low (2.5%, 2.0%, 2.6%, 1.2%, 1.8%, 1.5% and 1.7% during 1, 2, 3, 4, 5, 6 and 7 years of exposure to denosumab, respectively). The most common sites for nonvertebral fractures during the first 7 years in the extension were wrist (n = 91), hip (n = 26), ankle (n = 24), humerus (n = 23) and rib/clavicle (n = 20).
Effect on Bone Mineral Density (BMD)
Treatment with denosumab significantly increased BMD at all clinical sites measured at 1, 2, and 3 years. Denosumab increased lumbar spine BMD by 8.8%, total hip BMD by 6.4%, femoral neck BMD by 5.2%, and hip trochanter BMD by 8.3% over 3 years (all p < 0.0001).
In the long-term, open-label extension of Study 1, in women who received denosumab in Study 1 and continued on therapy (years 4 through 10 of denosumab treatment), denosumab treatment continued to increase BMD from extension baseline at the lumbar spine (10.8%; n = 1264), total hip (3.4%; n = 1232), femoral neck (3.8%; n = 1232) and trochanter (5.1%; n = 1232) in years 4 through 10. Percent increase in BMD from the original Study 1 baseline (ie, after 10 years of treatment) in the long-term group was 21.7% at the lumbar spine, 9.2% at the total hip, 9.0% at the femoral neck and 13.0% at the trochanter (all n = 1251). Annualized changes in BMD in the long-term, open-label extension portion of Study 1 are shown in Table 13.
Among women who crossed over to denosumab from placebo in Study 1, BMD gains from extension baseline were 16.5% (lumbar spine; n = 1223), 7.4% (total hip; n = 1200), 7.1% (femoral neck; n = 1200), and 10.3% (trochanter; n = 1200) after 7 years of denosumab administration. Annualized changes in BMD in the cross-over, open-label extension portion of Study 1 are shown in Table 13.
| Table 13. Bone Mineral Density Yearly Percent Change by Site in the Extension Study | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Long-term denosumab Group | Cross-over denosumab Group | |||||||||||||
| Exposure to denosumab | Lumbar Spine % (n) | Total Hip % (n) | Femoral Neck % (n) | Troch anter % (n) | Exposure to denosumab | Lumbar Spine % (n) | Total Hip % (n) | Femoral Neck % (n) | Troch anter % (n) | |||||
| Year 4 | 1.8 (2087) | 0.8 (2065) | 0.9 (2065) | 1.1 (2065) | Year 1 | 5.4 (1980) | 3.1 (1941) | 2.3 (1941) | 4.1 (1941) | |||||
| Year 5 | 1.7 (2017) | 0.6 (1998) | 0.4 (1998) | 0.9 (1998) | Year 2 | 2.5 (1898) | 1.1 (1870) | 1.1 (1870) | 1.4 (1870) | |||||
| Year 6 | 1.5 (1572) | 0.5 (1549) | 0.5 (1549) | 0.8 (1549) | Year 3 | 1.7 (1468) | 0.8 (1439) | 0.8 (1439) | 1.2 (1439) | |||||
| Year 7 | 1.6a (1361) | 0.4a (1330) | 0.6a (1330) | 0.6a (1330) | Year 4 | 1.8a (1281) | 0.7a (1252) | 0.8a (1252) | 0.9a (1252) | |||||
| Year 8 | Year 5 | |||||||||||||
| Year 9 | 1.6a (1245) | 0.4a (1206) | 0.5a (1206) | 0.7a (1206) | Year 6 | 1.8a (1206) | 0.6a (1174) | 0.7a (1174) | 0.9a (1174) | |||||
| Year 10 | Year 7 | |||||||||||||
a Annualized yearly change
n = Number of subjects with observed data at both time points of interest
Bone Histology and Histomorphometry
A total of 115 transiliac crest bone biopsy specimens were obtained from 92 postmenopausal women with osteoporosis at either month 24 and/or month 36 (53 specimens in denosumab group, 62 specimens in placebo group). Of the biopsies obtained, 115 (100%) were adequate for qualitative histology and 7 (6%) in the denosumab group were adequate for full quantitative histomorphometry assessment.
Qualitative histology assessments showed normal architecture and quality with no evidence of mineralization defects, woven bone, or marrow fibrosis in patients treated with denosumab.
Fifty-nine women participated in the bone biopsy sub-study at month 24 (N = 41) and/or month 84 (N = 22) of the extension study, representing up to 5 and 10 years of treatment with denosumab, respectively. Bone biopsy results showed bone of normal architecture and quality with no evidence of mineralization defects, woven bone or marrow fibrosis as well as the expected decrease in bone turnover.
The presence of double tetracycline labeling in a biopsy specimen provides an indication of active bone remodeling, while the absence of tetracycline label suggests suppressed bone formation. In subjects treated with denosumab, 35% had no tetracycline label present at the month 24 biopsy and 38% had no tetracycline label present at the month 36 biopsy, while 100% of placebo-treated patients had double label present at both time points. When compared to placebo, treatment with denosumab resulted in virtually absent activation frequency and markedly reduced bone formation rates. However, the long-term consequences of this degree of suppression of bone remodeling are unknown.
Treatment to Increase Bone Mass in Men with Osteoporosis at High Risk for Fracture
In men with osteoporosis, the efficacy and safety of denosumab were assessed in a randomized, double-blind, placebo-controlled study (Table 14).
| Table 14. Study 5 (ADAMO) | |||||||
|---|---|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (range) (yrs) | |||
| Study 5 (ADAMO) | Phase 3, randomized, double-blind, placebo-controlled | Denosumab 60 mg or placebo SC injection every 6 months (Q6M) (2 doses) | 242 men with osteoporosis (Denosumab: 121 Placebo: 121) | 65 (31, 84) | |||
The efficacy and safety of denosumab in increasing bone mass in men with osteoporosis was demonstrated in a 1-year, randomized, double-blind, placebo-controlled, multinational study of men with low bone mass, who had a baseline BMD T-score between –2.0 and –3.5 at the lumbar spine or femoral neck. Men with a BMD T-score between –1.0 and –3.5 at the lumbar spine or femoral neck and with history of prior fragility fracture were also enrolled. Men with other diseases (such as rheumatoid arthritis, osteogenesis imperfecta, and Paget’s disease) or on therapies that may affect bone were excluded from this study.
The 242 men enrolled in the study ranged in age from 31 to 84 years and were randomized to receive SC injections of either denosumab 60 mg (n = 121) or placebo (n = 121) once every 6 months. Patients also received at least 1000 mg calcium and at least 800 IU vitamin D supplementation daily.
Previous fractures in the denosumab and placebo groups were: 91 events in 47 patients (38.8%) vs. 76 events in 48 patients (39.7%) for any self-reported historical fractures since age 30, 18 events in 16 patients (13.2%) vs. 21 events in 20 patients (16.5%) for self-reported historical major osteoporotic fractures, and 43 events in 30 patients (24.8%) vs. 31 events in 25 patients (20.7%) for confirmed prevalent vertebral fractures, respectively.
The primary efficacy variable was percent change in lumbar spine BMD from baseline to 1 year. Secondary efficacy variables included percent change in total hip and femoral neck BMD from baseline to 1 year.
Effect on Bone Mineral Density (BMD)
Treatment with denosumab statistically significantly increased BMD at 1 year: the treatment differences in BMD at 1 year were: 4.8% (+5.7% denosumab, +0.9% placebo, p < 0.0001 [95% CI: 4.0%, 5.6%]) at the lumbar spine; 2.0% (+2.4% denosumab, +0.3% placebo) at the total hip; and 2.2% (+2.1% denosumab, 0.0% placebo) at femoral neck.
Consistent effects on BMD were observed at the lumbar spine regardless of baseline age, race, weight/body mass index (BMI), BMD, baseline testosterone levels and level of bone turnover.
The correlation between increased bone density and reduction of bone fracture in men with osteoporosis has not been established.
Bone Histology and Histomorphometry
The transiliac crest bone biopsy substudy enrolled 29/242 patients at selected study centres in Study 5 (17 specimens in denosumab group, 12 specimens in placebo group), after 12 months of treatment. Six (6) of the samples in the denosumab group were adequate for full quantitative histomorphometry assessment. Qualitative histology assessments showed normal architecture and quality with no evidence of mineralization defects, woven bone, or marrow fibrosis in patients treated with denosumab.
All subjects scheduled for the biopsy were to follow a double tetracycline/demeclocycline labelling procedure prior to undergoing the biopsy. The presence of double tetracycline labeling in a biopsy specimen provides an indication of active bone remodeling, while the absence of tetracycline label suggests suppressed bone formation. In patients treated with denosumab, 6% (n = 1) had no tetracycline label present at the month 12 biopsy, while 100% of placebo-treated patients (n = 12) had double label present. When compared to placebo, treatment with denosumab resulted in markedly reduced bone formation rates. However, the long-term consequences of this degree of suppression of bone remodeling are unknown.
Treatment to Increase Bone Mass in Men with Nonmetastatic Prostate Cancer receiving Androgen Deprivation Therapy (ADT), Who Are at High Risk for Fracture
| Table 15. Study 6 | ||||||||
|---|---|---|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (range) (yrs) | ||||
| Study 6 | Phase 3, randomized, double-blind, placebo-controlled | Denosumab 60 mg or placebo SC injection every 6 months for 3 years | 1468 patients with nonmetastatic prostate cancer (Denosumab: 734 Placebo: 734) | 75 (48, 97) | ||||
The efficacy and safety of denosumab in the treatment of bone loss in men with nonmetastatic prostate cancer receiving androgen deprivation therapy (ADT) were demonstrated in a 3 year, randomized (1:1), double-blind, placebo-controlled, multinational study (Table 15).
Men less than 70 years of age had either a BMD T-score at the lumbar spine, total hip, or femoral neck between -1.0 and -4.0, or a history of an osteoporotic fracture. The mean baseline lumbar spine BMD T-score was -0.4, and 22% of men had a vertebral fracture at baseline. The 1468 men enrolled ranged in age from 48 to 97 years (mean 75 years). Men were randomized to receive subcutaneous injections of either placebo (n = 734) or denosumab 60 mg (n = 734) once every 6 months for a total of 6 doses. Randomization was stratified by age (< 70 years vs. ≥ 70 years) and duration of ADT at trial entry (≤ 6 months vs. > 6 months). All men regardless of age had histologically confirmed prostate cancer. Seventy-nine percent of patients received ADT for more than 6 months at study entry. All men were instructed to take at least 1000 mg calcium and 400 IU vitamin D supplementation daily.
Effect on Bone Mineral Density (BMD)
The primary efficacy variable was percent change in lumbar spine BMD from baseline to month 24. Lumbar spine BMD was higher at 2 years in denosumab-treated patients as compared to placebo-treated patients [-1.0% placebo, +5.6% denosumab; treatment difference 6.7% (95% CI: 6.2, 7.1); p < 0.0001].
With approximately 62% of patients followed for 3 years, treatment differences in BMD at 3 years were 7.9% (-1.2% placebo, +6.8% denosumab) at the lumbar spine, 5.7% (-2.6% placebo, +3.2% denosumab) at the total hip, and 4.9% (-1.8% placebo, +3.0% denosumab) at the femoral neck (p < 0.0001). Consistent effects on BMD were observed at the lumbar spine in relevant subgroups defined by baseline age, race, geographical region, weight/BMI, BMD, level of bone turnover, duration of ADT, and baseline history of vertebral fracture.
Effect on Vertebral Fractures
An additional key secondary efficacy variable was the incidence of new vertebral fracture through month 36 diagnosed based on x-ray evaluation by two independent radiologists. The incidence of new vertebral fracture through month 12 and through month 24 were evaluated as exploratory endpoints. The subject-year adjusted incidence rate of new vertebral fractures at 3 years was 0.6 and 1.6 per 100 subject-years for denosumab and placebo, respectively. Denosumab significantly reduced the incidence of new vertebral fractures at 3 years (adjusted p = 0.0125). The relative risk reduction based on cumulative incidence of new vertebral fractures at 3 years was 62% (adjusted 95% Confidence Interval:13, 83) (2.4% absolute risk reduction; adjusted 95% Confidence Interval: 0.4, 4.4). The relative risk reduction of new vertebral fractures was 85% (1.6% absolute risk reduction) at 1 year and 69% (2.2% absolute risk reduction) at 2 years.
Treatment to Increase Bone Mass in Women Receiving Adjuvant AI Therapy for Nonmetastatic Breast Cancer Who Have Low Bone Mass and Are at High Risk for Fracture
| Table 16. Study 7 | ||||
|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (range) (yrs) |
| Study 7 | Phase 3, randomized, double-blind, placebo-controlled | Denosumab 60 mg or placebo SC injection every 6 months for 2 years | 252 patients with nonmetastatic breast cancer (Denosumab: 127 Placebo: 125) | 60 (35, 84) |
The efficacy and safety of denosumab in the treatment of bone loss in women receiving adjuvant aromatase inhibitor (AI) therapy for breast cancer was assessed in a 2 year, randomized (1:1), double-blind, placebo-controlled, multinational study (Table 16).
Women had baseline BMD T-scores between -1.0 to -2.5 at the lumbar spine, total hip, or femoral neck, and had not experienced fracture after age 25. The mean baseline lumbar spine BMD T-score was -1.1, and 2.0% of women had a vertebral fracture at baseline. The 252 women enrolled ranged in age from 35 to 84 years (mean 60 years). Women were randomized to receive subcutaneous injections of either placebo (n = 125) or denosumab 60 mg (n = 127) once every 6 months for a total of 4 doses. Randomization was stratified by duration of adjuvant AI therapy at trial entry (≤ 6 months vs. > 6 months). Sixty-two percent of patients received adjuvant AI therapy for more than 6 months at study entry. All women were instructed to take 1000 mg calcium and at least 400 IU vitamin D supplementation daily.
Effect on Bone Mineral Density (BMD)
The primary efficacy variable was percent change in lumbar spine BMD from baseline to month 12. Lumbar spine BMD was higher at 12 months in denosumab-treated patients as compared to placebo-treated patients [-0.7% placebo, +4.8% denosumab; treatment difference 5.5% (95% CI: 4.8, 6.3); p < 0.0001].
With approximately 81% of patients followed for 2 years, treatment differences in BMD at 2 years were 7.6% (-1.4% placebo, +6.2% denosumab) at the lumbar spine, 4.7 % (-1.0% placebo, +3.8% denosumab) at the total hip, and 3.6% (-0.8% placebo, +2.8% denosumab) at the femoral neck.
Treatment and Prevention of Glucocorticoid-Induced Osteoporosis (GIOP) in Men and Women at High Risk for Fracture
| Table 17. Study 8 | ||||||
|---|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study patients (n) | Mean age (range) (yrs) | ||
| Study 8 | Denosumab 60 mg SC injection once every 6 months or oral risedronate 5 mg once daily for 1 year | 795 patients (70% women, 30% men) Denosumab Glucocorticoid-initiating: 145 Glucocorticoid-continuing: 253 Risedronate Glucocorticoid-initiating: 145 Glucocorticoid-continuing: 252 | 63 (20,94) | |||
Men and women aged 20 to 94 years (mean age of 63 years) who were being treated with glucocorticoids (≥ 7.5 mg daily prednisone or its equivalent) for an expected duration of 6 months or longer for rheumatic, respiratory, skin, or other inflammatory diseases were enrolled (Table 17). Two subpopulations were studied: glucocorticoid-continuing (patients who received glucocorticoids for ≥ 3 months prior to screening; n = 505) and glucocorticoid-initiating (patients who received glucocorticoids for < 3 months prior to screening; n = 290). All enrolled patients < 50 years of age had a history of osteoporotic fracture. All enrolled patients ≥ 50
years of age who were in the glucocorticoid-continuing subpopulation had baseline bone mineral density (BMD) T-scores of ≤ -2.0 at the lumbar spine, total hip, or femoral neck; or a BMD T-score ≤ -1.0 at the lumbar spine, total hip, or femoral neck and a history of osteoporotic fracture.
Patients were randomized (1:1) to receive either denosumab 60 mg subcutaneously once every 6 months (n = 398) or oral risedronate 5 mg once daily (active control) (n = 397). Within each subpopulation, randomization was stratified by gender. All patients were instructed to take at least 1000 mg calcium and 800 IU vitamin D supplementation daily.
Effect on Bone Mineral Density (BMD)
The primary efficacy endpoint was percent change in lumbar spine BMD from baseline to month 12. In the glucocorticoid-continuing subpopulation, the percent change from baseline in lumbar spine BMD was higher at 1 year in denosumab-treated patients compared to risedronate-treated patients [(denosumab +4.4%, risedronate +2.3%; treatment difference 2.1% (95% CI: 1.4, 3.0, p <0.001)] (Table 18). In the glucocorticoid-initiating subpopulation, the percent change from baseline in lumbar spine BMD was higher at 1 year in denosumab-treated patients as compared to risedronate-treated patients [(denosumab +3.8%, risedronate + 0.8%; treatment difference 3.0% (95% CI: 2.0, 3.9, p <0.001)].
Consistent results for total hip BMD were observed in both subpopulations.
The correlation between increased bone mineral density and reduction of bone fracture incidence in patients with glucocorticoid-induced osteoporosis has not been directly established.
| Table 18. Results of Study 8 in Women and Men with Glucocorticoid-induced Osteoporosis at High Risk for Fracture (Denosumab vs. Risedronate) | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Sub-population | Location | Denosumab Mean % change in BMD after 1 year (95% CI) | Risedronate Mean % change in BMD after 1 year (95% CI) | Treatment Difference Mean (95% CI) | p-value | |||||
| Glucocorticoid-continuing | Lumbar Spine | 4.4 (3.8, 5.0) (N = 209) | 2.3 (1.7, 2.9) (N = 211) | 2.1 (1.4, 3.0) | < 0.001* | |||||
| Total hip | 2.1 (1.7, 2.5) (N = 217) | 0.6 (0.2, 1.0) (N = 215) | 1.5 (1.0, 2.1) | < 0.001* | ||||||
| Glucocorticoid-initiating | Lumbar Spine | 3.8 (3.1, 4.5) (N = 119) | 0.8 (0.2, 1.5) (N = 126) | 3.0 (2.0, 3.9) | < 0.001* | |||||
| Total hip | 1.7 (1.2, 2.2) (N = 119) | 0.2 (-0.2, 0.7) (N = 128) | 1.5 (0.8, 2.1) | < 0.001* | ||||||
* p-value adjusted for multiplicity within each subpopulation. Based on an ANCOVA model adjusting for treatment, baseline BMD, gender, machine type, and baseline BMD-by-machine type interaction. For glucocorticoid-continuing subpopulation, duration of prior glucocorticoid use (< 12 months vs ≥ 12 months) was included as an additional covariate.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Denosumab is a potent inhibitor of osteoclastic bone resorption via inhibition of RANK ligand (RANKL).
In ovariectomized monkeys, once-monthly treatment with denosumab suppressed bone turnover and caused significant gain in BMD, and strength of cancellous and cortical bone. Bone tissue was normal with no evidence of mineralization defects, accumulation of osteoid, or woven bone.
Transition from 6-month alendronate treatment to denosumab in monkeys did not cause any meaningful decreases in serum calcium and significantly increased or maintained BMD of the whole body, lumbar spine, and distal radius. Bone strength parameters at these sites were maintained or improved with transition to denosumab, relative to continuous treatment with alendronate. Bone strength and reduction in bone resorption at all skeletal sites were maintained or improved in monkeys switched from alendronate to denosumab.
Since the biological activity of denosumab in animals is specific to non-human primates, evaluation of genetically engineered (“knockout”) mice or use of other biological inhibitors of the RANK/RANKL pathway, namely OPG-Fc, provided additional information on the pharmacodynamic properties of denosumab. RANK/RANKL knockout mice exhibited impairment of lymph node formation, had an absence of lactation due to inhibition of mammary gland maturation (lobulo-alveolar gland development during pregnancy), and exhibited reduced bone growth and lack of tooth eruption. Similar phenotypic changes were seen in a corroborative study in 2-week old rats given the RANK ligand inhibitor OPG-Fc. After 10 weeks on study, these changes were partially reversible in this model when dosing with the RANKL inhibitors was discontinued. Refer to Table 19 Summary of Preclinical Toxicity and Reproductive Studies with Denosumab for details of the individual study results.
Carcinogenicity
Since denosumab is highly species-specific and is not active in rodents, traditional rodent cancer bioassays could not be performed. RANKL inhibition (the target of denosumab) has been studied in a wide range of short-term animal models of cancer and shown no carcinogenic potential. Additionally, RANKL inhibition has shown no evidence of immunosuppression in a wide range of animal models.
Genotoxicity
The genotoxic potential of denosumab has not been evaluated. Denosumab is a recombinant protein made up entirely of naturally-occurring amino acids and contains no inorganic or synthetic organic linkers or other non-protein portions. Therefore, it is unlikely that denosumab or any of its derived fragments would react with DNA or other chromosomal material.
Reproductive and Developmental Toxicology
Denosumab had no effect on female fertility or male reproductive organs in monkeys at exposures that were 100- to 150-fold higher than the human exposure for 60 mg SC administered once every 6 months (see Tables 19 and 20).
| Table 19. Summary of Preclinical Toxicity and Reproductive Studies with Denosumab | |||||||
|---|---|---|---|---|---|---|---|
| Type of Study | Species and strain | Number per sex per group | Route of Administration | Dose (mg/kg) and dosing regimen | Study Duration | Treatment-related findings | NOAEL (mg/kg) |
| Repeated- dose Toxicity | Cynomolgus monkey | 6 | Subcutaneous (SC) or Intravenous (IV) | Once weekly: 0, 0.1, 1.0, & 10.0 (SC); 10.0 (IV) | 1 month dosing with 3 months recovery | Consistent with the pharmacological action of denosumab, there were rapid and marked decreases in circulating markers of bone turnover at all doses. Correlating with these changes, there was increased bone mineral density in males dosed at 1 and 10 mg/kg. With the exception of bone mineral density which tended to be maintained, these changes were recovered or recovering following 3 treatment-free months. There were no treatment related effects on organ weights or histopathology findings | 10 (SC and IV) |
| Cynomolgus monkey | 8 | Subcutaneous | Once monthly: 0, 1, 10, 50 | 6 and 12 months with 3 months recovery | Consistent with the pharmacological action of denosumab, there were rapid and marked decreases in circulating markers of bone turnover at 10 and 50 mg/kg. Correlating to these changes, there was increased bone mineral density, bone mineral content, cortical area and thickness, and bone strength parameters in males dosed at 50 mg/kg, and females dosed at 10 and 50 mg/kg. In addition, there was enlargement of the growth plates, decreased osteoblasts and osteoclasts, and decreased chondroclasis at 10 and 50 mg/kg. These changes were recovered or recovering following 3 treatment-free months. There were no treatment related changes in opthalmoscopy, cardiovascular physiology, sperm motility and morphology, circulating immunoglobulins and lymphocyte subsets, or organ weights. | 50 | |
| Female Fertility | Cynomolgus monkey | 6 females | Subcutaneous | Once weekly: 0, 2.5, 5, 12.5 | Over 2 menstrual cycles before mating and for 4 weeks after mating | No treatment related effects on cyclicity, circulating reproductive hormones, mating success. | 12.5 |
| Table 19. Summary of Preclinical Toxicity and Reproductive Studies with Denosumab | |||||||
|---|---|---|---|---|---|---|---|
| Type of Study | Species and strain | Number per sex per group | Route of Administration | Dose (mg/kg) and dosing regimen | Study Duration | Treatment-related findings | NOAEL (mg/kg) |
| Embryo-fetal Development | Cynomolgus monkey | 16 females | Subcutaneous | Once weekly: 0, 2.5, 5, 12.5 | Gestation days 20-50 | No treatment related effects on mother or embryonic development were observed. Peripheral lymph nodes were not evaluated. | 12.5 |
| Enhanced pre- and post-natal development | Cynomolgus monkey | 29 females | Subcutaneous | Once monthly: 0, 50 | Gestation days 20-22 to birth | There were increased fetal losses during gestation, increased stillbirths and post-natal mortality (see Table 20.). Treatment-related findings in the offspring included decreased body weight gain and decreased neonatal growth; skeletal abnormalities resulting from impaired bone resorption during rapid growth, including bones at the base of the skull resulting in altered cranial shape and exophthalmos, reduced bone strength and treatment-related bone fractures; reduced hematopoiesis; decreased serum levels of bone resorption and bone formation biomarkers; tooth malalignment and dental dysplasia (in the absence of adverse effects on tooth eruption); infections; and absence of peripheral lymph nodes. Following a recovery period from birth out to 6 months of age, findings still observed were mildly reduced bone length (femoral, vertebral, jaw), reduced cortical thickness with associated reduced strength; extramedullary hematopoiesis; dental dysplasia; and the absence or decreased size of some lymph nodes. One infant had minimal to moderate mineralization in multiple tissues. The initially lower growth rates returned to, but never exceeded the growth rate in the control group, and hence, the infants exposed to denosumab remained smaller than control infants, as measured by body weight and morphometric measurements. For the denosumab-treated maternal animals, there was a decrease in serum levels of bone resorption and formation biomarkers, and serum alkaline phosphatase levels; recovery was evident by the end of the treatment-free period. Maternal mammary gland development was normal. At birth out to 1 month of | A NOAEL was not identified |
| Table 19. Summary of Preclinical Toxicity and Reproductive Studies with Denosumab | |||||||
|---|---|---|---|---|---|---|---|
| Type of Study | Species and strain | Number per sex per group | Route of Administration | Dose (mg/kg) and dosing regimen | Study Duration | Treatment-related findings | NOAEL (mg/kg) |
| age, infants had measurable blood levels of denosumab (22-621% of maternal levels). Only one infant had measurable concentrations of denosumab on BD91, and no infants had measurable concentrations on BD180. Generally, the effects observed in mothers and infants were consistent with the pharmacological action of denosumab. | |||||||
| Safety Pharmacology | Cynomolgus monkey | 3 males | Subcutaneous | Single dose: 0, 0.3, 3, 30 | 7 days | No treatment related effects on heart rate, blood pressure, electrical activity of the heart, or respiratory rate were observed. | 30 |
| Sprague Dawley weanling rats | 71 males and 67 females | Subcutaneous | Rat OPG-Fc: 1, 10 mg/kg/ week Murine RANK-Fc: 10 mg/kg/ week | 6 weeks | Increased bone volume, density and strength. Increased cancellous bone with reduced osteoclast number. Reduced long bone growth with altered growth plate morphology and increased thickness. Impaired tooth eruption and tooth root formation. | N/A | |
| Sprague Dawley neonatal rats | 51 males and 49 females | Subcutaneous | Rat OPG-Fc or ALN: 5 μL/g/week for 6 weeks followed by 10 week treatment-free period | 16 weeks | Ten weeks after the discontinuation of a 6-week course of OPG-Fc administration, neonatal rats exhibited evidence of restored bone resorption and partial normalization of bone density, size, and strength. Molar eruption, which had been substantially delayed during the administration of OPG-Fc, exhibited partial recovery in some animals within 10 weeks of its discontinuation. The relative increases in bone volume, density, and strength that occurred during 6 weeks of ALN administration were generally preserved 10 weeks after its discontinuation, whereas molar eruption did not recover within this timeframe. Modest epiphyseal growth plate changes persisted 10 weeks after discontinuing high-dose OPG-Fc. Bone size, body weight, and molar root development remained significantly reduced 10 weeks after discontinuation of OPG-Fc or ALN when compared to the vehicle control group. | N/A | |
| Table 19. Summary of Preclinical Toxicity and Reproductive Studies with Denosumab | |||||||
|---|---|---|---|---|---|---|---|
| Type of Study | Species and strain | Number per sex per group | Route of Administration | Dose (mg/kg) and dosing regimen | Study Duration | Treatment-related findings | NOAEL (mg/kg) |
| Other Studies – Tissue Cross-reactivity | Cynomolgus monkey, rat, rabbit | N/A | In Vitro | 5 or 25 μg/mL | N/A | Staining of lymphoid tissue in rabbit and cynomolgus monkey and staining of chondrocytes in rat were observed. | N/A |
| Cynomolgus monkey, human | N/A | In Vitro | 1 or 10 μg/mL | N/A | Staining of lymphoid tissue in monkey, but no staining in human tissue was observed. | N/A | |
| Human | N/A | In Vitro | 1 or 10 μg/mL | N/A | Staining of lymphoid tissue was observed. | N/A | |
N/A = not applicable; NOAEL = No Observed Adverse Effect Level
| Table 20. Total Fetal Lossesc, all Groups | |||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Dose, (mg/kg) | Total No. Pregnant Females; Infants Born (M/F) | Gestation Day (GD) of Fetal Loss | % Fetal Loss by Dose Level | ||||||||||||||
| Full Gestation | First Trimester (GD20 to GD50) | Third Trimester Total (≥GD100) | Third Trimester Stillbirths (≥GD140) | ||||||||||||||
| 0 | 29; 22 (13/9) | GDs 32, 32, 33, 104, 152, 157, 170 | 24.1% (7/29) | 10.3% (3/29) | 13.8% (4/29) | 10.3% (3/29) | |||||||||||
| 50 | 29; 16 (7/9) | GDs 31, 32, 33, 33, 46, 88a, 132, 151, 156a, 157, 158, 160, 168 | 40.7% (11/27) 44.8%** (13/29) | 17.2% (5/29) | 22.2% (6/27) 24.1%** (7/29) | 18.5% (5/27) 20.7%** (6/29) | |||||||||||
| Historical Control Datab | 24.8% (33/133) | 6.8% (9/133) | 15.8% (21/133) | 9.0% (12/133) | |||||||||||||
| Range | (6.7 to 38.9%) | (0 to 11.8%) | (0 to 28.6%) | (0 to 16.7%) | |||||||||||||
a Two adult females were excluded from fetal loss calculations except for first trimester because each had an anti -drug antibody (ADA) response beginning at GD76 with subsequent decrease in pharmacologic effect (bone biomarkers) prior to fetal loss; results indicated by a double asterisk (**) include these ADA-positive adult fe-males.
b Based on 8 enhanced PPND studies conducted at the Testing Facility from 2008 to 2010.
c Fetal losses occurring prior to GD140 were considered abortions; those occurring on or after GD140 were consid -ered stillbirths.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PROLIA® (denosumab injection), 60 mg / mL solution for injection, submission control # 276666, Product Monograph, Amgen Canada Inc. November 24, 2023