


Product Monograph - Juluca
Recent Major Label Changes
| Section | Date |
|---|---|
| 4 Dosage and Administration, 4.1 Dosing Considerations | 11/2024 |
| 7 Warnings and Precautions, General | 07/2023 |
| 7 Warnings and Precautions, Reproductive Health | 11/2024 |
| 7 Warnings and Precautions, 7.1.1 Pregnancy | 11/2024 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................. 2
Table of Contents .................................................................................................................. 2
Part 1: Healthcare Professional Information........................................................................... 4
1 Indications ................................................................................................................. 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 Contraindications ....................................................................................................... 4
4 Dosage and Administration ........................................................................................ 4
4.1 Dosing Considerations ............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.5 Missed Dose ............................................................................................................. 5
5 Overdose ................................................................................................................... 5
6 Dosage Forms, Strengths, Composition, and Packaging ............................................... 6
7 Warnings and Precautions .......................................................................................... 6
General ................................................................................................................................ 6
Depressive Disorders .......................................................................................................... 6
Hepatoxicity ........................................................................................................................ 7
Risk of Adverse Reactions or Loss of Virologic Response Due to Drug Interactions .......... 7
Skin and Hypersensitivity reactions .................................................................................... 7
Reproductive Health ........................................................................................................... 8
7.1 Special Populations .................................................................................................. 8
7.1.1 Pregnancy ............................................................................................................. 8
7.1.2 Breastfeeding ..................................................................................................... 10
7.1.3 Pediatrics ............................................................................................................ 10
7.1.4 Geriatrics ............................................................................................................ 10
8 Adverse Reactions .................................................................................................... 10
8.1 Adverse Reaction Overview ................................................................................... 10
8.2 Clinical Trial Adverse Reactions ............................................................................. 10
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 11
8.3.1 Less Common Clinical Trial Adverse Reactions (Pediatrics) ............................... 12
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .............................................................................................................. 12
8.5 Post-Market Adverse Reactions ............................................................................ 13
9 Drug Interactions ..................................................................................................... 14
9.2 Drug Interactions Overview ................................................................................... 14
9.4 Drug-Drug Interactions .......................................................................................... 14
9.5 Drug-Food Interactions .......................................................................................... 21
9.6 Drug-Herb Interactions .......................................................................................... 21
9.7 Drug-Laboratory Test Interactions ........................................................................ 21
10 Clinical Pharmacology .............................................................................................. 21
10.1 Mechanism of Action ............................................................................................. 21
10.2 Pharmacodynamics................................................................................................ 22
10.3 Pharmacokinetics .................................................................................................. 22
11 Storage, Stability, and Disposal ................................................................................. 26
Part 2: Pharmaceutical Information ..................................................................................... 27
13 Pharmaceutical Information ..................................................................................... 27
14 Clinical Trials ............................................................................................................ 28
14.1 Clinical Trials by Indication .................................................................................... 28
14.2 Comparative Bioavailability Studies ...................................................................... 31
15 Microbiology ............................................................................................................ 33
16 Non-Clinical Toxicology ............................................................................................ 36
17 Supporting Product Monographs .............................................................................. 37
Patient Medication Information .......................................................................................... 38
Part 1: Healthcare Professional Information
1 Indications
JULUCA (dolutegravir/rilpivirine) is indicated as a complete regimen to replace the current antiretroviral regimen for:
- the treatment of human immunodeficiency virus (HIV-1) infection in adults who are virologically stable and suppressed (HIV-1 RNA less than 50 copies per mL).
1.1 Pediatrics
Pediatrics (< 18 years of age): Safety and efficacy of JULUCA have not been established in pediatric patients less than 18 years of age.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Clinical studies of JULUCA did not include sufficient numbers of patients aged 65 years and older to determine whether they respond differently from adult patients < 65 years of age.
2 Contraindications
JULUCA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
JULUCA is contraindicated in combination with the following (see 9 Drug Interactions):
- Drugs with narrow therapeutic windows, that are substrates of organic cation transporter 2 (OCT2), including but not limited to dofetilide, an antiarrhythmic agent, or the potassium channel blocker fampridine (also known as dalfampridine)
- Carbamazepine, oxcarbazepine, phenobarbital, and phenytoin; anticonvulsants
- rifampin, rifapentine; antimycobacterials
- proton pump inhibitors omeprazole, esomeprazole, lansoprazole, pantoprazole, and rabeprazole
- systemic dexamethasone (more than a single-dose); glucocorticoid
- St John’s wort (Hypericum perforatum) (see 9.6 Drug-Herb Interactions)
4 Dosage and Administration
4.1 Dosing Considerations
- As with all antiretroviral drugs, therapy should be initiated by a healthcare professional experienced in the management of HIV infection.
- JULUCA should not be used in patients with known or suspected resistance to dolutegravir or rilpivirine.
- Prior to initiating JULUCA, patients should be on stable antiretroviral therapy for at least 6 months.
4.2 Recommended Dose and Dosage Adjustment
Adults
The recommended dose of JULUCA in adults is one tablet once daily taken orally with a meal (see 10.3 Pharmacokinetics).
Pediatrics (< 18 years of age): Safety and efficacy of JULUCA have not been established in pediatric patients less than 18 years of age.
Geriatrics (≥ 65 years of age): Clinical studies of JULUCA did not include sufficient numbers of patients aged 65 years and older to determine whether they respond differently from adult patients < 65 years of age.
Rifabutin Coadministration
If JULUCA is coadministered with rifabutin, take an additional 25 mg tablet of EDURANT (rilpivirine) with JULUCA once daily with a meal for the duration of the rifabutin coadministration (see Table 4).
Renal insufficiency
No dosage adjustment of JULUCA is required in patients with renal insufficiency (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Hepatic insufficiency
No dosage adjustment of JULUCA is required in patients with mild or moderate hepatic insufficiency (Child-Pugh score A or B). JULUCA has not been studied in patients with severe hepatic insufficiency (Child-Pugh score C) (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
4.5 Missed Dose
If the patient misses a dose of JULUCA, the patient should take it with a meal as soon as they remember if it is more than 12 hours until the next dose. If the next dose is due within 12 hours, the patient should skip the missed dose and resume the usual dosing schedule.
5 Overdose
Symptoms and signs
Experience with overdose of JULUCA or the individual components, dolutegravir and rilpivirine is limited.
Treatment
There is no known specific treatment for overdose with JULUCA. If overdose occurs, the patient should be monitored and standard supportive treatment applied as required, including monitoring of vital signs, ECG (QT interval), and observation of the clinical status of the patient. As dolutegravir and rilpivirine are highly bound to plasma proteins, it is unlikely they will be significantly removed by dialysis.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition, and Packaging
Table 1 Dosage Forms, Strengths, Composition and Packaging.
Each film coated tablet of JULUCA contains 50 mg dolutegravir (as 52.6 mg of dolutegravir sodium) and 25 mg rilpivirine (as 27.5 mg rilpivirine hydrochloride).
Dosage Forms
JULUCA tablets are pink, film-coated, oval, biconvex tablets debossed with ‘SV J3T’ on one side.
Packaging
JULUCA tablets are supplied in white HDPE (high density polyethylene) bottles closed with polypropylene child-resistant closures. Each bottle contains 30 film-coated tablets and a silica gel desiccant.
7 Warnings and Precautions
General
As with other antiretroviral medicinal products, resistance testing and/or historical resistance data should guide the use of JULUCA. JULUCA should not be used in patients with known or suspected resistance to dolutegravir or rilpivirine. The SWORD studies excluded patients who had not been on stable antiretroviral therapy for at least 6 months.
Patients receiving JULUCA or any other antiretroviral therapy may still develop opportunistic infections and other complications of HIV infection. Therefore patients should remain under close clinical observation by physicians experienced in the treatment of these associated HIV diseases.
Depressive Disorders
Depressive disorders (including depressed mood, depression, dysphoria, major depression, mood altered, negative thoughts, suicide attempt, and suicidal ideation) have been reported with other rilpivirine-containing products (see 8 Adverse Reactions). Promptly evaluate patients with severe depressive symptoms to assess whether the symptoms are related to JULUCA and to determine whether the risks of continued therapy outweigh the benefits.
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | tablet/ 50 mg dolutegravir (as dolutegravir sodium), 25 mg rilpivirine (as rilpivirine hydrochloride) | croscarmellose sodium, D-mannitol, iron oxide red, iron oxide yellow, lactose monohydrate, macrogol/PEG, magnesium stearate, microcrystalline cellulose, polysorbate 20, polyvinyl alcohol-part hydrolyzed, povidone K29/32 and K30, silicified microcrystalline cellulose, sodium starch glycolate, sodium stearyl fumarate, talc, titanium dioxide |
Hepatoxicity
Hepatic adverse events have been reported in patients receiving other rilpivirine or other dolutegravir-containing regimens. Patients with underlying hepatitis B or C or marked elevations in transaminases prior to treatment may be at increased risk for worsening or development of transaminase elevations with use of rilpivirine or dolutegravir. A few cases of hepatic toxicity have been reported in adult patients receiving other rilpivirine or other dolutegravir-containing regimens who had no pre-existing hepatic disease or other identifiable risk factors. Drug-induced liver injury leading to liver transplant has been reported with TRIUMEQ (dolutegravir/abacavir/lamivudine). Appropriate laboratory testing prior to initiating therapy and monitoring for hepatotoxicity during therapy with JULUCA is recommended.
Risk of Adverse Reactions or Loss of Virologic Response Due to Drug Interactions
The concomitant use of JULUCA and other drugs may result in known or potentially significant drug interactions, some of which may lead to (see 2 Contraindications, 9 Drug Interactions):
- Loss of therapeutic effect of JULUCA and possible development of resistance.
- Possible clinically significant adverse reactions from greater exposures of concomitant drugs.
In healthy subjects, 75 mg once daily rilpivirine (3 times the dose in JULUCA) and 300 mg once daily (12 times the dose in JULUCA) have been shown to prolong the QTc interval of the electrocardiogram (see 2 Contraindications, 9 Drug Interactions, 10 Clinical Pharmacology). Consider alternatives to JULUCA when coadministered with a drug with a known risk of Torsade de Pointes. See Table 4 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations. Consider the potential for drug interactions prior to and during therapy with JULUCA; review concomitant medications during therapy with JULUCA; and monitor for the adverse reactions associated with the concomitant drugs.
Skin and Hypersensitivity reactions
Hypersensitivity reactions have been reported with integrase inhibitors, including dolutegravir, and were characterized by rash, constitutional findings, and sometimes organ dysfunction, including liver injury.
Severe skin and hypersensitivity reactions have been reported during postmarketing experience with other rilpivirine-containing regimens, including cases of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS). While some skin reactions were accompanied by constitutional symptoms such as fever, other skin reactions were associated with organ dysfunctions, including elevations in hepatic serum biochemistries. During the Phase 3 clinical trials of rilpivirine, treatment-related rashes with at least Grade 2 severity were reported in 3% of patients. No Grade 4 rash was reported. Overall, most rashes were Grade 1 or 2 and occurred in the first 4 to 6 weeks of therapy (see 8 Adverse Reactions).
During the Phase 3 clinical trials with dolutegravir plus rilpivirine, treatment-related rashes were reported in approximately 1% of patients, and all were Grade 1 or 2.
Discontinue JULUCA and other suspect agents immediately if signs or symptoms of severe skin or hypersensitivity reactions develop (including, but not limited to, severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters or peeling of the skin, mucosal involvement [oral blisters or lesions], conjunctivitis, facial edema, hepatitis, eosinophilia, angioedema, difficulty breathing). Clinical status, including laboratory parameters with liver aminotransferases, should be monitored and appropriate therapy initiated. Delay in stopping treatment with JULUCA or other suspect agents after the onset of hypersensitivity may result in a life-threatening reaction (see 2 Contraindications).
Reproductive Health
- Fertility
There are no data on the effects of dolutegravir and/or rilpivirine on human male or female fertility. Animal studies indicate no effects of dolutegravir or rilpivirine on male or female fertility (see 16 Non-Clinical Toxicology).
7.1 Special Populations
7.1.1 Pregnancy
There is limited information on the use of JULUCA in pregnancy. JULUCA should not be used in pregnant women unless the potential benefits outweigh the potential risks to the fetus.
There are insufficient human data on the use of JULUCA during pregnancy to definitively assess a drug-associated risk for birth defects and miscarriage. However, available human data from the Antiretroviral Pregnancy Registry (APR) with the individual components of JULUCA do not indicate an increased risk of birth defects (see Information on individual components). In the Canadian general population, the estimated background rate for major birth defects and miscarriage in clinically recognized pregnancies is 3% to 5% and 15% to 25%, respectively.
Information on individual components
Dolutegravir:
Two large birth outcome surveillance studies in Botswana (Tsepamo) and Eswatini, which together include over 19,000 individuals taking dolutegravir-containing regimens at conception, show no significant difference in neural tube defect prevalence in infants born to individuals taking dolutegravir at conception compared to those born to individuals taking non-dolutegravir containing antiretroviral regimens at conception, or infants born to HIV-negative individuals.
The first interim analysis from the Tsepamo birth outcome surveillance study in Botswana identified an association between dolutegravir and an increased risk of neural tube defects when dolutegravir was administered at the time of conception and in early pregnancy. A subsequent analysis was conducted based on a larger cohort from the birth outcome surveillance study in Botswana and included over 9,460 individuals exposed to dolutegravir at conception, 23,664 individuals exposed to non-dolutegravir-containing regimens, and 170,723 HIV negative pregnant individuals. The prevalence of neural tube defects in infants delivered to individuals taking dolutegravir at conception was 0.11% (95% CI: 0.05-0.19%). The observed prevalence rate did not differ significantly from that of infants delivered to individuals taking non-dolutegravir-containing regimens (0.11%, 95% CI: 0.07-0.16%), or to HIV-negative individuals (0.06%, 95% CI: 0.05-0.08%).
The Eswatini birth outcome surveillance study includes 9,743 individuals exposed to dolutegravir at conception, 1,838 individuals exposed to non-dolutegravir-containing regimens, and 32,259 HIV-negative pregnant individuals. The prevalence of neural tube defects in infants delivered to individuals taking dolutegravir at conception was 0.08% (95% CI: 0.04-0.16%). The observed prevalence rate did not differ significantly from that of infants delivered to individuals taking non-dolutegravir-containing regimens (0.22%, 95% CI: 0.06-0.56%) or to HIV-negative individuals (0.08%, 95% CI: 0.06-0.12%). The observed prevalence of neural tube defects in infants delivered to individuals taking non-dolutegravir-containing regimens had a wide confidence interval due to low sample size.
Limitations of these birth outcome surveillance studies include insufficient data to determine if baseline characteristics were balanced between the study groups or to assess other factors such as the use of folic acid during the preconception or first trimester periods.
Based on prospective reports to the APR of 1,378 exposures to dolutegravir during pregnancy resulting in live births (including 874 exposed in the first trimester), there was no difference between the overall risk of birth defects for dolutegravir when compared to the background birth defect rate from two population based surveillance systems (Metropolitan Atlanta Congenital Defects Program (MACDP) with defects of 2.72 per 100 live births and the Texas Birth Defects Registry (TBDR) with 4.17 per 100 live births). The prevalence of defects in live births was 3.3% (95% CI: 2.2% to 4.7%) following first trimester exposure to dolutegravir-containing regimens and 5.0% (95% CI: 3.2% to 7.3%) following second/third trimester exposure to dolutegravir-containing regimens.
Dolutegravir readily crosses the placenta in humans. In pregnant women with HIV, the median (range) fetal umbilical cord concentrations of dolutegravir were 1.28 (1.21 to 1.28) fold greater compared with maternal peripheral plasma concentrations.
There is insufficient information on the effects of dolutegravir on neonates.
In reproductive toxicity studies in animals, no evidence of teratogenicity, reproductive function, relevant embryonic or fetal toxicity, including neural tube defects, was identified in rats and rabbits at ≥30 and 0.55 times human clinical exposure based on AUC, respectively (see 16 Non-Clinical Toxicology).
Rilpivirine:
Rilpivirine in combination with a background regimen was evaluated in a clinical trial of 19 pregnant women during the second and third trimesters, and postpartum. The pharmacokinetic data demonstrate that total exposure (AUC) to rilpivirine as a part of an antiretroviral regimen was approximately 30% lower during pregnancy compared with postpartum (6-12 weeks). Virologic response was preserved throughout the trial period. No mother to child transmission occurred in all 10 infants born to the mothers who completed the trial and for whom the HIV status was available. Rilpivirine was well tolerated during pregnancy and postpartum. There were no new safety findings compared with the known safety profile of rilpivirine in HIV-1 infected adults (see 10.3 Pharmacokinetics, Special Populations and Conditions, Pregnancy and Postpartum).
Based on prospective reports to the APR of over 870 exposures to rilpivirine during pregnancy resulting in live births (including 660 exposed in the first trimester), there was no difference between the overall risk of birth defects for rilpivirine compared with the background birth defect rates of 2.72% and 4.17% from the MACDP and TBDR, respectively. The prevalence of defects in live births was 2.1% (95% CI: 1.1% to 3.5%) and 0.9% (95% CI: 0.1% to 3.4%) following first and second/third trimester exposure, respectively, to rilpivirine-containing regimens.
Studies in rats and rabbits with rilpivirine have shown no evidence of relevant embryonic or fetal toxicity, effect on reproductive function, or teratogenicity (see 16 Non-Clinical Toxicology).
Antiretroviral Pregnancy Registry (APR): To monitor maternal-fetal outcomes of pregnant women with HIV exposed to JULUCA and other antiretroviral agents, an Antiretroviral Pregnancy Registry has been established. Healthcare professionals are encouraged to register patients:
http://www.apregistry.com
Telephone: (800) 258-4263
Fax: (800) 800-1052
7.1.2 Breastfeeding
HIV-1-infected mothers should not breast-feed their infants to avoid risking postnatal transmission of HIV. Dolutegravir is excreted in human milk in small amounts. In an open-label randomised study in which HIV- infected treatment-naïve pregnant women were administered a dolutegravir based regimen until two weeks post-partum, the median (range) dolutegravir breast milk to maternal plasma ratio was 0.033 (0.021 to 0.050). It is not known if rilpivirine is present in human milk. HIV-1-infected mothers should be instructed not to breast-feed if they are receiving JULUCA.
7.1.3 Pediatrics
Pediatrics (<18 years): Safety and efficacy of JULUCA have not been established in pediatric patients less than 18 years of age.
7.1.4 Geriatrics
Geriatrics (≥65 years): Clinical studies of JULUCA did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from adult patients less than 65 years of age.
8 Adverse Reactions
8.1 Adverse Reaction Overview
The safety assessment of JULUCA in HIV-1-infected, virologically suppressed patients switching from their current antiretroviral regimen to dolutegravir plus rilpivirine is based on the pooled primary Week 48 analyses of data from 2 identical, international, multicenter, open-label studies: SWORD-1 and SWORD-2, including additional follow-up through week 148. For details on adverse reactions that have occurred in studies with EDURANT or TIVICAY, please refer to the respective product monographs.
A total of 1,024 adult HIV-1-infected patients who were on a stable suppressive antiretroviral regimen (containing 2 NRTIs plus either an INSTI, an NNRTI, or a PI) were randomized and received treatment. Patients were randomized 1:1 to continue their current antiretroviral regimen or be switched to dolutegravir plus rilpivirine administered once daily (Early Switch). Subjects initially randomized to continue their current antiretroviral regimen and who remained virologically suppressed at Week 48 switched to dolutegravir plus rilpivirine at Week 52 (Late Switch). The rates of adverse events leading to discontinuation in the pooled analysis through week 48 were 4% in patients receiving dolutegravir plus rilpivirine once daily and less than 1% in patients who remained on their current antiretroviral regimen. The most common adverse events leading to discontinuation through week 48 were psychiatric disorders; 2% of patients receiving dolutegravir plus rilpivirine and less than 1% on the current antiretroviral regimen. In the pooled analyses, the rate of adverse events leading to discontinuation through Week 148 was 8%.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
There were no treatment-emergent adverse drug reactions (ADRs) (Grades 2 to 4) with an incidence of at least 2% in either treatment arm. ADRs (all Grades) observed in at least 2% of patients in either treatment arm of the pooled analysis of the SWORD-1 and SWORD-2 trials are provided in Table 2. The ADRs observed for dolutegravir plus rilpivirine in the Week 48 analysis of the pooled data from Phase 3 clinical trials were consistent with the ADR profiles and severities for the individual components when administered with other antiretroviral agents. No additional ADRs or increased frequency or severity of ADRs were observed with the combination of dolutegravir plus rilpivirine.
Table 2 Treatment-Emergent Adverse Drug Reactions (Grades 1 to 4) and at Least 2% Frequency in Virologically Suppressed Patients (Week 48 Pooled Analyses)
| SOC | SWORD 1 DTG plus RPV (n = 252) n (%) | SWORD 1 CAR (n=256) n (%) | SWORD 2 DTG plus RPV (n = 261) n (%) | SWORD 2 CAR (n=255) n (%) | POOLED DTG plus RPV (n = 513) n (%) | POOLED CAR (n = 511) n (%) |
|---|---|---|---|---|---|---|
| Gastrointestinal | ||||||
Diarrhea Abdominal Distension Nausea Flatulence | 4 (2%) 5 (2%) 4 (2%) 1 (<1%) | 1 (<1%) 0 0 0 | 4 (2%) 2 (<1%) 3 (1%) 5 (2%) | 0 0 0 0 | 8 (2%) 7 (1%) 7 (1%) 6 (1%) | 1 (<1%) 0 0 0 |
| General Disorders | ||||||
| Fatigue | 5 (2%) | 0 | 0 (0%) | 0 | 5 (<1%) | 0 |
| Nervous System | ||||||
Headache Dizziness | 5 (2%) 2 (<1%) | 0 1 (<1%) | 6 (2%) 4 (2%) | 0 0 | 11 (2%) 6 (1%) | 0 1 (<1%) |
SOC = System Organ Class/Preferred Term, CAR = current antiretroviral therapy, DTG = dolutegravir, RPV = rilpivirine
In the Week 148 pooled analyses, nausea and headache (all grades) were observed in 2% of patients (n = 8 and n = 11, respectively) who received DTG plus RPV from study start.
8.3 Less Common Clinical Trial Adverse Reactions
The following ADRs occurred in less than 2% of patients receiving dolutegravir plus rilpivirine or are from studies described in the product monographs of the individual components TIVICAY (dolutegravir) and EDURANT (rilpivirine). Some events have been included because of their seriousness and assessment of potential causal relationship.
Gastrointestinal Disorders: Abdominal pain, abdominal discomfort, flatulence, nausea, upper abdominal pain, vomiting.
General Disorders: Fatigue.
Hepatobiliary Disorders: Cholecystitis, cholelithiasis, hepatitis.
Immune System Disorders: Hypersensitivity, Immune reconstitution inflammatory syndrome.
Metabolism and Nutrition Disorders: Decreased appetite.
Musculoskeletal Disorders: Myalgia, Myositis.
Nervous System Disorders: Dizziness, somnolence.
Psychiatric Disorders: Anxiety, depressed mood, depression, insomnia, abnormal dreams, sleep disorders, suicidal ideation or suicide attempt (particularly in patients with a pre-existing history of depression or psychiatric illness).
Renal and Urinary Disorders: Glomerulonephritis membranous, glomerulonephritis, mesangioproliferative, nephrolithiasis, renal insufficiency.
Skin and Subcutaneous Tissue Disorders: Pruritus, rash.
8.3.1 Less Common Clinical Trial Adverse Reactions (Pediatrics)
There are no clinical study data with JULUCA in the pediatric population.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Selected laboratory abnormalities with a worsening grade from baseline and representing the worst-grade toxicity experienced in at least 2% of patients are presented in Table 3.
Table 3 Selected Laboratory Abnormalities (Grades 2 and 3 to 4; Week 48 Pooled Analyses)
Laboratory Parameter Preferred Term | Dolutegravir plus Rilpivirine (n = 513) n (%) | Current Antiretroviral Regimen (n = 511) n (%) |
|---|---|---|
| ALT | ||
| Grade 2 (>2.5-5.0 x ULN) | 8 (2%) | 4 (<1%) |
| Grade 3 to 4 (>5.0 x ULN) | 3 (<1%) | 3 (<1%) |
| AST | ||
| Grade 2 (>2.5-5.0 x ULN) | 5 (<1%) | 8 (2%) |
| Grade 3 to 4 (>5.0 x ULN) | 3 (<1%) | 4 (<1%) |
| Total Bilirubin | ||
| Grade 2 (1.6-2.5 x ULN) | 11 (2%) | 18 (4%) |
| Grade 3 to 4 (>2.5 x ULN) | 0 | 13 (3%) |
| Creatine kinase | ||
| Grade 2 (6.0-9.9 x ULN) | 4 (<1%) | 5 (<1%) |
| Grade 3 to 4 (≥10.0 x ULN) | 6 (1%) | 11 (2%) |
| Hyperglycemia | ||
| Grade 2 (126-250 mg/dL) | 21 (4%) | 26 (5%) |
| Grade 3 to 4 (>250 mg/dL) | 5 (<1%) | 1 (<1%) |
| Hypophosphataemia | ||
| Grade 2 (0.45 <0.65 mmol/L) | 44 (9%) | 79 (15%) |
| Grade 3 to 4 (<0.32 mmol/L) | 3 (<1%) | 11 (2%) |
| Lipase | ||
| Grade 2 (>1.5-3.0 x ULN) | 25 (5%) | 24 (5%) |
| Grade 3 to 4 (>3.0 x ULN) | 11 (2%) | 11 (2%) |
ULN = Upper limit of normal.
For subjects in the pooled Early Switch DTG+RPV and Late Switch DTG+RPV groups through Week 148, the majority of post-Baseline emergent clinical chemistry toxicities were Grade 1 or Grade 2 in intensity and the proportions of subjects with any Grade 3 or Grade 4 clinical chemistry toxicities were 4% or less.
Serum Lipids: No clinically relevant changes in lipid profiles were noted throughout the 48 weeks in either treatment arm, or beyond Week 48.
Changes in Serum Creatinine: Increases in serum creatinine occurred within the first four weeks of treatment with dolutegravir plus rilpivirine and remained stable through 148 weeks. Mean (SD) changes from baseline of 8.22 μmol/L (9.41) and 9.86 μmol/L (10.40) were observed after 48 weeks and 148 weeks of treatment, respectively. These changes are related to inhibition of active transport, and are not considered to be clinically relevant as they do not reflect a change in glomerular filtration rate (see 10.2 Pharmacodynamics, Effects on Renal Function).
Small increases in total bilirubin (without clinical jaundice) were observed with dolutegravir plus rilpivirine. These changes are not considered clinically relevant as they likely reflect competition between dolutegravir and unconjugated bilirubin for a common clearance pathway (UGT1A1) (see 10.3 Pharmacokinetics, Metabolism).
Co-infection with Hepatitis B or C: A higher incidence of Grade 1 liver chemistry elevations was observed in patients treated with dolutegravir plus rilpivirine co-infected with hepatitis C compared with those who were not co-infected. JULUCA has not been studied in patients with hepatitis B co-infection.
Bone Mineral Density Effects
Mean bone mineral density (BMD) increased from baseline to Week 48 in subjects who switched from an antiretroviral treatment (ART) regimen containing tenofovir disoproxil fumarate (TDF) to dolutegravir plus rilpivirine (1.34% total hip and 1.46% lumbar spine) compared with those who continued on treatment with a TDF-containing antiretroviral regimen (0.05% total hip and 0.15% lumbar spine, p = 0.014 and p = 0.039, respectively) in a dual-energy X-ray absorptiometry (DXA) substudy. BMD declines of 5% or greater at the lumbar spine were experienced by 2% of subjects receiving JULUCA and 5% of subjects who continued their TDF-containing regimen. The long-term clinical significance of these BMD changes is not known.
Fractures (excluding fingers and toes) were reported in 3 (0.6%) subjects who switched to dolutegravir plus rilpivirine and 9 (1.8%) subjects who continued their current antiretroviral regimen through 48 weeks.
Adrenal Function
In the pooled Phase 3 trials results analysis of rilpivirine, at Week 96, there was an overall mean change from baseline in basal cortisol of -0.69 (-1.12, 0.27) micrograms/dL in the rilpivirine group and of -0.02 (-0.48, 0.44) micrograms/dL in the efavirenz group. The clinical significance of the higher abnormal rate of 250 micrograms ACTH stimulation tests in the rilpivirine group is not known. Refer to the EDURANT (rilpivirine) Prescribing Information for additional information.
8.5 Post-Market Adverse Reactions
These events have been chosen for inclusion due to either their seriousness, frequency of reporting, potential causal connection to dolutegravir- or rilpivirine-containing regimens, or a combination of these factors. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
Blood and Lymphatic Systems Disorders: sideroblastic anaemia. Reversible sideroblastic anaemia has been reported with dolutegravir-containing regimens (the contribution of dolutegravir in these cases is unclear).
Hepatobiliary Disorders: Acute liver failure, hepatotoxicity
Musculoskeletal and connective disorders: arthralgia, myalgia
Renal and Genitourinary Disorders: Nephrotic syndrome
Skin and Subcutaneous Tissue Disorders: Severe skin and hypersensitivity reactions including DRESS (see 7 Warnings and Precautions).
Investigations: weight increased
9 Drug Interactions
9.2 Drug Interactions Overview
JULUCA contains dolutegravir plus rilpivirine and any interactions that have been identified with either component individually may occur with JULUCA. There are no significant drug interactions between dolutegravir and rilpivirine. Because JULUCA is a complete regimen, coadministration with other antiretroviral medications for the treatment of HIV-1 infection is not recommended. Information regarding potential drug-drug interactions with other antiretroviral medications is not provided. For more information on these interactions, please refer to the EDURANT and TIVICAY product monographs.
9.4 Drug-Drug Interactions
In vitro, dolutegravir inhibited the renal organic cation transporters, (OCT)2 (IC50 = 1.93 µM), multidrug and toxin extrusion transporter (MATE)-1 (IC50 = 6.34 micromolar) and MATE2-K (IC50 = 24.8 micromolar). In vivo, dolutegravir has a low potential to affect the transport of MATE2-K substrates. In vivo, dolutegravir inhibits tubular secretion of creatinine by inhibiting OCT2. Dolutegravir may increase plasma concentrations of drugs in which excretion is dependent upon OCT2 (for example dofetilide, fampridine (also known as dalfampridine) [see 2 Contraindications], metformin) or MATE1 (see Table 4).
In vitro, dolutegravir inhibited the basolateral renal transporters: organic anion transporter (OAT) 1 (IC50 = 2.12 micromolar) and OAT3 (IC50 = 1.97 micromolar). Based upon the dolutegravir unbound plasma concentration, in silico modelling and lack of notable effect on the in vivo pharmacokinetics of the OAT substrates tenofovir and para aminohippurate, dolutegravir has a low propensity to cause drug interactions via inhibition of OAT transporters.
Effect of Other Agents on the Pharmacokinetics of Dolutegravir or Rilpivirine
Dolutegravir
Dolutegravir is metabolized by UGT1A1 with some contribution from CYP3A. Dolutegravir is also a substrate of UGT1A3, UGT1A9, CYP3A4, Pgp, and BCRP in vitro; therefore drugs that induce those enzymes and transporters, may decrease dolutegravir plasma concentrations and reduce the therapeutic effect of dolutegravir.
Co-administration of dolutegravir and other drugs that inhibit UGT1A1, UGT1A3, UGT1A9, CYP3A4, and/or Pgp may increase dolutegravir plasma concentrations (see Table 4).
In vitro, dolutegravir is not a substrate of human OATP1B1, OATP1B3, or OCT1.
Coadministration of dolutegravir with polyvalent cation-containing products may lead to decreased absorption of dolutegravir.
Rilpivirine
Rilpivirine is primarily metabolized by CYP3A, and medicinal products that induce or inhibit CYP3A may thus affect the clearance of rilpivirine (see 10.3 Pharmacokinetics). Co-administration of rilpivirine with medicinal products that induce CYP3A may result in decreased plasma concentrations of rilpivirine which could potentially reduce the therapeutic effect of rilpivirine. Co-administration of rilpivirine and medicinal products that inhibit CYP3A may result in increased plasma concentrations of rilpivirine.
Coadministration of JULUCA with drugs that increase gastric pH may result in decreased plasma concentrations of rilpivirine and loss of virologic response and possible resistance to rilpivirine or to the class of NNRTIs.
QT-Prolonging Drugs: In healthy subjects, 75 mg once daily rilpivirine (3 times the dose in JULUCA) and 300 mg once daily (12 times the dose in JULUCA) have been shown to prolong the QTc interval of the electrocardiogram (see 10.2 Pharmacodynamics, Effects on Electrocardiogram). Consider alternatives to JULUCA when coadministered with a drug with a known risk of Torsade de Pointes.
Established or Potential Drug Interactions
Established and theoretical interactions with selected antiretrovirals and non-antiretroviral medicinal products are listed in Table 4. The drugs listed in this table are not all-inclusive. Recommendations are based on either drug interaction studies, or potential or predicted interactions due to the expected magnitude of interaction and/or potential for serious adverse events or loss of efficacy.
Table 4 Established or Potential Drug-Drug Interactions
Concomitant Drug Class: Drug Name | Effect on Concentration of Dolutegravir, Rilpivirine, or Concomitant Drug* | Clinical comment | |
Concomitant Drug Class: Drug Name | Effect on Concentration of Dolutegravir, Rilpivirine, or Concomitant Drug* | Clinical comment | |
Concomitant Drug Class: Drug Name | Effect on Concentration of Dolutegravir, Rilpivirine, or Concomitant Drug* | Clinical comment | |
Antiarrhythmic: Dofetilide | Effect of dolutegravir: Dofetilide ↑ | Co-administration of JULUCA with dofetilide is contraindicated due to potential life-threatening toxicity caused by high dofetilide concentrations. | |
Potassium channel blocker: Fampridine (also known as dalfampridine | Fampridine/Dalfampridine↑ | Co-administration is contraindicated with JULUCA due to potential for seizures associated with fampridine/dalfampridine. | |
Anticonvulsants: Carbamazepine, Oxcarbazepine, Phenytoin, Phenobarbital | Effect of carbamazepine: Dolutegravir ↓ Rilpivirine ↓ | Co-administration is contraindicated. | |
Proton Pump Inhibitors: Omeprazole† Lansoprazole Rabeprazole Pantoprazole Esomeprazole | Dolutegravir ↔ Rilpivirine ↓ (by omeprazole) Omeprazole ↓ (by rilpivirine) | Co-administration is contraindicated. | |
H2-Receptor Antagonists: Famotidine† Cimetidine Nizatidine Ranitidine | Dolutegravir ↔ Famotidine taken 12 hrs before Rilpivirine: Rilpivirine↔ Famotidine taken 2 hrs before Rilpivirine: Rilpivirine ↓ Famotidine taken 4 hrs after Rilpivirine: | JULUCA should be administered at least 4 hours before or at least 12 hours after H2-receptor antagonists. | |
| Rilpivirine ↔ | |||
| Antacids (e.g. aluminium or, magnesium hydroxide, and/or calcium carbonate: | Dolutegravir ↓ Rilpivirine ↓ | JULUCA should be administered at least 4 hours before or 6 hours after taking antacids. | |
Medications containing polyvalent cations (e.g. Mg or Al): Cation-containing productsb or laxatives Sucralfate Buffered medications | Dolutegravir ↓ | JULUCA should be administered at least 4 hours before or 6 hours after taking products containing polyvalent cations. | |
| Calcium and Iron supplements, including multivitamins containing calcium or ironb (Non-antacid) | Calcium: Dolutegravir ↓ Iron: Dolutegravir ↓ | When taken with food, JULUCA and calcium and/or iron supplements or multivitamins containing calcium and/or iron can be taken at the same time. Under fasting conditions, JULUCA should be taken at least 4 hours before or 6 hours after taking calcium or iron supplements (non-antacids). | |
Antidiabetics: Metforminb | Co-administered with dolutegravir: Metformin ↑ Co-administered with rilpivirine: Metformin ↔ | Consider metformin dose adjustments when starting or stopping concomitant treatment to maintain glycemic control. | |
Rifampin† Rifapentine | Dolutegravir ↓ Rifampin ↔ Rilpivirine ↓ | Co-administration is contraindicated. | |
Antimycobacterials: Rifabutinb | Dolutegravir ↔ Rifabutin ↔ Rilpivirine ↓ | Rifabutin decreased the plasma concentrations of rilpivirine. An additional rilpivirine 25 mg tablet should be taken with JULUCA once daily with a meal when rifabutin is co-administered. | |
| Dexamethasone (systemic, except for single dose use) | Rilpivirine ↓ Dolutegravir ↔ | Co-administration is contraindicated, except for single dose use. | |
Narcotic analgesics: Methadoneb | Effect of dolutegravir: Methadone ↔ Effect of rilpivirine: R(-), S(+) Methadone ↓ | No dose adjustment is necessary. However, clinical monitoring is recommended as methadone maintenance therapy may need to be adjusted in some patients. | |
Azole Antifungals: Ketoconazole† Fluconazole Itraconazole Posaconazole Voriconazole | Dolutegravir ↔ Rilpivirine ↑ Ketoconazole ↓ | No dose adjustment is necessary. | |
Macrolide or ketolide antibiotics: Clarithromycin Erythromycin Telithromycin | Dolutegravir ↔ Rilpivirine ↑ | No dose adjustment is necessary. | |
Legend; ↑ = Increase; ↓ =decrease; ↔ = no significant change
† This interaction study has been performed with a dose higher than the recommended dose for rilpivirine assessing the maximal effect on the co-administered drug
b See Tables 5 to 8 for magnitude of interaction
The effects of DTG and RPV on the exposure of co-administered drugs are shown in Table 5 and Table 7, respectively. The effects of co-administered drugs on the exposure of DTG and RPV are shown in Table 6 and Table 8, respectively.
Table 5 Summary of Effect of Dolutegravir on the Pharmacokinetics of Co-administered Drugs
Co-administered Drug(s) and Dose(s) | Dose of Dolutegravir | n | Geometric Mean Ratio (90% CI) of Pharmacokinetic Parameters of Co-administered Drug With/Without Dolutegravir No Effect = 1.00 | |||||||||||
| Cτ or C24 | AUC | Cmax | ||||||||||||
Daclatasvir 60 mg once daily | 50 mg once daily | 12 | 1.06 (0.88 to 1.29) | 0.98 (0.83 to 1.15) | 1.03 (0.84 to 1.25) | |||||||||
Ethinyl estradiol 0.035 mg | 50 mg twice daily | 15 | 1.02 (0.93, 1.11) | 1.03 (0.96, 1.11) | 0.99 (0.91, 1.08) | |||||||||
Methadone 16 to 150 mg | 50 mg twice daily | 12 | 0.99 (0.91, 1.07) | 0.98 (0.91, 1.06) | 1.00 (0.94, 1.06) | |||||||||
Midazolam 3 mg | 25 mg once daily | 10 | _ | 0.95 (0.79, 1.15) | _ | |||||||||
Norgestimate 0.25 mg | 50 mg twice daily | 15 | 0.93 (0.85, 1.03) | 0.98 (0.91, 1.04) | 0.89 (0.82, 0.97) | |||||||||
Rilpivirine 25 mg once daily | 50 mg once daily | 16 | 1.21 (1.07, 1.38) | 1.06 (0.98, 1.16) | 1.10 (0.99, 1.22) | |||||||||
Metformin 500 mg twice daily | 50 mg once daily | 14 | _ | 1.79 (1.65, 1.93) | 1.66 (1.53, 1.81) | |||||||||
Metformin 500 mg twice daily | 50 mg twice daily | 14 | _ | 2.45 (2.25, 2.66) | 2.11 (1.91, 2.33) | |||||||||
Table 6 Summary of Effect of Co-administered Drugs on the Pharmacokinetics of Dolutegravir
Co-administered Drug(s) and Dose(s) | Dose of Dolutegravir | n | Geometric Mean Ratio (90% CI) of Dolutegravir Pharmacokinetic Parameters With/Without Co-administered Drugs No Effect = 1.00 | ||||||||||
Co-administered Drug(s) and Dose(s) | Dose of Dolutegravir | n | Geometric Mean Ratio (90% CI) of Dolutegravir Pharmacokinetic Parameters With/Without Co-administered Drugs No Effect = 1.00 | ||||||||||
| Cτ or C24 | AUC | Cmax | |||||||||||
| Cτ or C24 | AUC | Cmax | |||||||||||
| Maalox® | 50 mg single dose | 16 | 0.26 (0.21, 0.31) | 0.26 (0.22, 0.32) | 0.28 (0.23, 0.33) | ||||||||
Maalox® 2 hrs after dolutegravir | 50 mg single dose | 16 | 0.70 (0.58, 0.85) | 0.74 (0.62, 0.90) | 0.82 (0.69, 0.98) | ||||||||
Calcium Carbonate 1200 mg simultaneous administration (fasted) | 50 mg single dose | 12 | 0.61 (0.47, 0.80) | 0.61 (0.47, 0.80) | 0.63 (0.50, 0.81) | ||||||||
Calcium Carbonate 1200 mg simultaneous administration (fed) | 50 mg single dose | 11 | 1.08 (0.81, 1.42) | 1.09 (0.84, 1.43) | 1.07 (0.83, 1.38) | ||||||||
Calcium Carbonate 1200 mg 2 hrs after dolutegravir | 50 mg single dose | 11 | 0.90 (0.68, 1.19) | 0.94 (0.72, 1.23) | 1.00 (0.78, 1.29) | ||||||||
Ferrous Fumarate 324 mg simultaneous administration (fasted) | 50 mg single dose | 11 | 0.44 (0.36, 0.54) | 0.46 (0.38, 0.56) | 0.43 (0.35, 0.52) | ||||||||
Ferrous Fumarate 324 mg simultaneous administration n (fed) | 50 mg single dose | 11 | 1.00 (0.81, 1.23) | 0.98 (0.81, 1.20) | 1.03 (0.84, 1.26) | ||||||||
Ferrous Fumarate 324 mg 2 hrs after dolutegravir | 50 mg single dose | 10 | 0.92 (0.74, 1.13) | 0.95 (0.77, 1.15) | 0.99 (0.81, 1.21) | ||||||||
Multivitamin One tablet once daily | 50 mg single dose | 16 | 0.68 (0.56, 0.82) | 0.67 (0.55 , 0.81) | 0.65 (0.54, 0.77) | ||||||||
Omeprazole 40 mg once daily | 50 mg single dose | 12 | 0.95 (0.75, 1.21) | 0.97 (0.78, 1.20) | 0.92 (0.75, 1.11) | ||||||||
Prednisone 60 mg once daily with taper | 50 mg once daily | 12 | 1.17 (1.06, 1.28) | 1.11 (1.03, 1.20) | 1.06 (0.99, 1.14) | ||||||||
Rifampina 600 mg once daily | 50 mg twice dailya | 11 | 0.28 (0.23, 0.34) | 0.46 (0.38, 0.55) | 0.57 (0.49, 0.65) | ||||||||
Rifampinb 600 mg once daily | 50 mg twice dailyb | 11 | 1.22 (1.01, 1.48) | 1.33 (1.15, 1.53) | 1.18 (1.03, 1.37) | ||||||||
Rifabutin 300 mg once daily | 50 mg once daily | 9 | 0.70 (0.57, 0.87) | 0.95 (0.82, 1.10) | 1.16 (0.98, 1.37) | ||||||||
Rilpivirine 25 mg once daily | 50 mg once daily | 16 | 1.22 (1.15, 1.30) | 1.12 (1.05, 1.19) | 1.13 (1.06, 1.21) | ||||||||
Carbamazepine 300 mg twice daily | 50 mg once daily | 14 | 0.27 (0.24, 0.31) | 0.51 (0.48, 0.55) | 0.67 (0.61, 0.73) | ||||||||
Daclatasvir 60 mg once daily | 50 mg once daily | 12 | 1.45 (1.25 to 1.68) | 1.33 (1.11 to 1.59) | 1.29 (1.07 to 1.57) | ||||||||
a Comparison is rifampin taken with dolutegravir 50 mg twice daily compared with dolutegravir 50 mg twice daily.
b Comparison is rifampin taken with dolutegravir 50 mg twice daily compared with dolutegravir 50 mg once daily.
Table 7 Summary of Effect of Rilpivirine on the Pharmacokinetics of Co-administered Drugs
| Co-administered Drug(s) and Dose(s) | Dose of Rilpivirine | n | Geometric Mean Ratio (90% CI) of Co-administered Drug Pharmacokinetic Parameters with/without EDURANT No Effect = 1.00 | ||||||
| Co-administered Drug(s) and Dose(s) | Dose of Rilpivirine | n | Geometric Mean Ratio (90% CI) of Co-administered Drug Pharmacokinetic Parameters with/without EDURANT No Effect = 1.00 | ||||||
| Cmin | AUC | Cmax | |||||||
| Cmin | AUC | Cmax | |||||||
Acetaminophen 500 mg single dose | 150 mg once dailya | 16 | NA | 0.91 (0.86, 0.97) | 0.97 (0.86, 1.10) | ||||
Atorvastatin 40 mg once daily | 150 mg once dailya | 16 | 0.85 (0.69, 1.03) | 1.04 (0.97, 1.12) | 1.35 (1.08, 1.68) | ||||
Chlorzoxazone 500 mg single dose taken 2 hours after rilpivirine | 150 mg once dailya | 16 | NA | 1.03 (0.95, 1.13) | 0.98 (0.85, 1.13) | ||||
Digoxin 0.5 mg single dose | 25 mg once daily | 22 | NA | 0.98 (0.93, 1.04)c | 1.06 (0.97, 1.17) | ||||
Ethinylestradiol 0.035 mg once daily | 25 mg once daily | 17 | 1.09 (1.03, 1.16) | 1.14 (1.10, 1.19) | 1.17 (1.06, 1.30) | ||||
Norethindrone 1 mg once daily | 0.99 (0.90, 1.08) | 0.89 (0.84, 0.94) | 0.94 (0.83, 1.06) | ||||||
Ketoconazole 400 mg once daily | 150 mg once dailya | 14 | 0.34 (0.25, 0.46) | 0.76 (0.70, 0.82) | 0.85 (0.80, 0.90) | ||||
Methadone 60-100 mg once daily, individualized dose | 25 mg once daily | 13 | |||||||
| R(-) methadone | 0.78 (0.67, 0.91) | 0.84 (0.74, 0.95) | 0.86 (0.78, 0.95) | ||||||
| S(+) methadone | 0.79 (0.67, 0.92) | 0.84 (0.74, 0.96) | 0.87 (0.78, 0.97) | ||||||
Metformin 850 mg single dose | 25 mg once daily | 20 | NA | 0.97 (0.90, 1.06)b | 1.02 (0.95, 1.10) | ||||
Omeprazole 20 mg once daily | 150 mg once dailya | 15 | NA | 0.86 (0.76, 0.97) | 0.86 (0.68, 1.09) | ||||
Rifabutin 300 mg once daily | 150 mg Once daily a | 17 | 1.01 (0.94, 1.09) | 1.03 (0.97,1.09) | 1.03 (0.93,1.14) | ||||
Rifampin 600 mg once daily | 150 mg once dailya | 16 | NA | 0.99 (0.92, 1.07) | 1.02 (0.93, 1.12) | ||||
Sildenafil 50 mg single dose | 75 mg once dailya | 16 | NA | 0.97 (0.87, 1.08) | 0.93 (0.80, 1.08) | ||||
CI = Confidence Interval; n = Maximum number of patients with data; NA = Not available.
a This interaction study has been performed with a dose higher than the recommended dose for rilpivirine (25 mg once daily) assessing the maximal effect on the co-administered drug
b N (maximum number of patients with data) for AUC(0-∞) = 15
c AUC(0-last)
Table 8 Summary of Effect of Co-administered Drugs on the Pharmacokinetics of Rilpivirine
Co-administered Drug(s) and Dose(s) | Dose of Rilpivirine | n | Geometric Mean Ratio (90% CI) of Rilpivirine Pharmacokinetic Parameters with/without Co-administered Drugs No Effect = 1.00 | ||||||
Co-administered Drug(s) and Dose(s) | Dose of Rilpivirine | n | Geometric Mean Ratio (90% CI) of Rilpivirine Pharmacokinetic Parameters with/without Co-administered Drugs No Effect = 1.00 | ||||||
| Cmin | AUC | Cmax | |||||||
| Cmin | AUC | Cmax | |||||||
Acetaminophen 500 mg single dose | 150 mg once dailya | 16 | 1.26 (1.16, 1.38) | 1.16 (1.10, 1.22) | 1.09 (1.01, 1.18) | ||||
Atorvastatin 40 mg once daily | 150 mg once dailya | 16 | 0.90 (0.84, 0.96) | 0.90 (0.81, 0.99) | 0.91 (0.79, 1.06) | ||||
Chlorzoxazone 500 mg single dose taken 2 hours after rilpivirine | 150 mg once dailya | 16 | 1.18 (1.09, 1.28) | 1.25 (1.16, 1.35) | 1.17 (1.08, 1.27) | ||||
Ethinylestradiol/ Norethindrone 0.035 mg once daily/ 1 mg once daily | 25 mg once daily | 15 | ↔b | ↔b | ↔b | ||||
Famotidine 40 mg single dose taken 12 hours before rilpivirine | 150 mg single dosea | 24 | N.A. | 0.91 (0.78, 1.07) | 0.99 (0.84, 1.16) | ||||
Famotidine 40 mg single dose taken 2 hours before rilpivirine | 150 mg single dosea | 23 | N.A. | 0.24 (0.20, 0.28) | 0.15 (0.12, 0.19) | ||||
Famotidine 40 mg single dose taken 4 hours after rilpivirine | 150 mg single dosea | 24 | N.A. | 1.13 (1.01, 1.27) | 1.21 (1.06, 1.39) | ||||
Ketoconazole 400 mg once daily | 150 mg once dailyb | 15 | 1.76 (1.57, 1.97) | 1.49 (1.31, 1.70) | 1.30 (1.13, 1.48) | ||||
Methadone 60-100 mg once daily, individualised dose | 25 mg once daily | 12 | ↔b | ↔b | ↔b | ||||
Omeprazole 20 mg once daily | 150 mg once dailya | 16 | 0.67 (0.58, 0.78) | 0.60 (0.51, 0.71) | 0.60 (0.48, 0.73) | ||||
Rifabutin 300 mg once daily | 25 mg once daily | 18 | 0.52 (0.46, 0.59) | 0.58 (0.52, 0.65) | 0.69 (0.62, 0.76) | ||||
Rifabutin 300 mg once daily | 50 mg once daily | 18 | 0.93 (0.85, 1.01) | 1.16 (1.06, 1.26) | 1.43 (1.30, 1.56) | ||||
| (as compared to 25 mg once daily rilpivirine alone) | |||||||||
Rifampin 600 mg once daily | 150 mg once dailya | 16 | 0.11 (0.10, 0.13) | 0.20 (0.18, 0.23) | 0.31 (0.27, 0.36) | ||||
Sildenafil 50 mg single dose | 75 mg once dailya | 16 | 1.04 (0.98, 1.09) | 0.98 (0.92, 1.05) | 0.92 (0.85, 0.99) | ||||
CI = Confidence Interval; n = Maximum number of patients with data; N.A. = Not available; ↔ = No change.
a This interaction study has been performed with a dose higher than the recommended dose for rilpivirine (25 mg once daily) assessing the maximal effect on the co-administered drug
b Comparison based on historic controls
9.5 Drug-Food Interactions
JULUCA must be taken with a meal to ensure optimal rilpivirine plasma concentration. A protein-rich nutritional drink or meal replacement drink is not considered a meal (see 10 Clinical Pharmacology). The effect of a high fat, high calorie meal on the absorption of dolutegravir and rilpivirine when administered as a fixed-dose combination tablet has not been assessed in an appropriately designed study.
9.6 Drug-Herb Interactions
Co-administration of JULUCA with products containing St. John’s wort may significantly decrease dolutegravir and rilpivirine plasma concentrations, resulting in loss of therapeutic effect. Co-administration of JULUCA with products containing St. John’s wort is contraindicated.
9.7 Drug-Laboratory Test Interactions
No Drug-Laboratory test interactions have been identified.
10 Clinical Pharmacology
10.1 Mechanism of Action
Dolutegravir inhibits HIV integrase by binding to the integrase active site and blocking the strand transfer step of retroviral Deoxyribonucleic acid (DNA) integration which is essential for the HIV replication cycle. Strand transfer biochemical assays using purified HIV 1 integrase and pre-processed substrate DNA resulted in IC50 values of 2.7 nM and 12.6 nM. In vitro, dolutegravir dissociates slowly from the active site of the wild type integrase-DNA complex (t½ 71 hours).
Rilpivirine is a diarylpyrimidine non-nucleoside reverse transcriptase inhibitor (NNRTI) of HIV-1. Rilpivirine activity is mediated by non-competitive inhibition of HIV-1 reverse transcriptase (RT). Rilpivirine does not inhibit the human cellular DNA polymerases α, β and γ.
10.2 Pharmacodynamics
In a randomized, dose-ranging trial, HIV-1-infected patients treated with dolutegravir monotherapy demonstrated rapid and dose-dependent antiviral activity with mean declines from baseline to Day 11 in HIV-1 RNA of 1.5, 2.0, and 2.5 log10 for dolutegravir 2 mg, 10 mg, and 50 mg once daily, respectively. This antiviral response was maintained for 3 to 4 days after the last dose in the 50-mg group.
Effects on Electrocardiogram
Dolutegravir
In a randomized, placebo-controlled, cross-over trial, 42 healthy subjects received single dose oral administrations of placebo, dolutegravir 250 mg suspension (exposures approximately 3-fold of the 50 mg once-daily dose at steady state), and moxifloxacin (400 mg, active control) in random sequence. Dolutegravir did not prolong the QTc interval for 24 hours post dose. After baseline and placebo adjustment, the maximum mean QTc change based on Fridericia correction method (QTcF) was 1.99 msec (1-sided 95% upper CI: 4.53 msec).
Rilpivirine
The effect of rilpivirine at the recommended dose of 25 mg once daily on the QTcF interval was evaluated in a randomised, placebo and active (moxifloxacin 400 mg once daily) controlled crossover study in 60 healthy adults. Rilpivirine at the recommended dose of 25 mg once daily is not associated with a clinically relevant effect on QTc. The maximum mean time-matched (95% upper confidence bound) differences in QTcF interval from placebo after baseline correction was 2.0 (5.0) msec (i.e., below the threshold of clinical concern).
When supratherapeutic doses of 75 mg and 300 mg once daily of rilpivirine were studied in healthy adults, the maximum mean time-matched (95% upper confidence bound) differences in QTcF interval from placebo after baseline correction were 10.7 (15.3) and 23.3 (28.4) ms, respectively. Steady-state administration of rilpivirine 75 mg and 300 mg once daily resulted in a mean Cmax approximately 2.6-fold and 6.7-fold, respectively, higher than the mean steady-state Cmax observed with the 25 mg once daily dose of rilpivirine.
Effects on Renal Function
The effect of dolutegravir on serum creatinine clearance (CrCl), glomerular filtration rate (GFR) using iohexol as the probe and effective renal plasma flow (ERPF) using para-aminohippurate (PAH) as the probe was evaluated in an open-label, randomized, 3 arm, parallel, placebo-controlled study in 37 healthy subjects, who were administered dolutegravir 50 mg once daily (n=12), 50 mg twice daily (n=13) or placebo once daily (n=12) for 14 days. A modest decrease in CrCl was observed with dolutegravir within the first week of treatment, consistent with that seen in clinical studies. Dolutegravir at both doses had no significant effect on GFR or ERPF. These data support in vitro studies which suggest that the small increases in creatinine observed in clinical studies are due to the nonpathologic inhibition of the organic cation transporter 2 (OCT2) in the proximal renal tubules, which mediates the tubular secretion of creatinine.
10.3 Pharmacokinetics
The pharmacokinetic (PK) properties of the components of JULUCA are provided in Table 9.
Table 9 Pharmacokinetic Properties of the Components of JULUCA
| Dolutegravir | Rilpivirine | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Absorption | |||||||||||
| AUCT a (ng.h/mL) | 68166.3 (24.4) | 3349.4 (36.5) | |||||||||
| Cmax a (ng/mL) | 3703.3 (17.5) | 100.1 (33.6) | |||||||||
| Tmax (h)b | 3.0 (0.5 – 6.0) | 4.0 (1.0 – 9.0) | |||||||||
| Effect of moderate fat meal (relative to fasting) on AUC (%) c | 187.5 (154.7 – 227.4) | 157.1 (123.6 – 199.8) | |||||||||
| Effect of moderate fat meal (relative to fasting) on Cmax (%) c | 174.9 (140.3 – 218.1) | 189.1 (133.9 – 266.9) | |||||||||
| Effect of high fat meal (relative to fasting) | Not assessedd | ||||||||||
| Distribution | |||||||||||
| % Bound to human plasma proteins | ~99 | ~99 | |||||||||
| Source of protein binding data | in vitro | in vitro | |||||||||
| Blood-to-plasma ratio | 0.5 | 0.7 | |||||||||
| Metabolism | |||||||||||
| Primarily metabolized | UGT1A1 CYP3A (minor) | CYP3A | |||||||||
| Elimination | |||||||||||
| Major route of elimination | Metabolism | Metabolism | |||||||||
| t1/2 (h)a | 15.0 (19.2%) | 59.2 (45.7) | |||||||||
| % of dose excreted as total 14C (unchanged drug) in urinee | 31 (<1) | 6.5 (<1) | |||||||||
| % of dose excreted as total 14C (unchanged drug) in fecese | 64 (53) | 85 (25) | |||||||||
a Arithmetic mean (CV%) after single dose administration with a moderate fat meal (see 14.2 Comparative Bioavailability Studies). Moderate fat meal [~625 kcal: 125 kcal from protein (20%), 300 kcal from carbohydrate (48%), and 200 kcal from fat (32%)]. AUCT= AUC0-120 for dolutegravir and AUC0-264 for rilpivirine
b Median (range) after single dose administration with a moderate fat meal (see 14.2 Comparative Bioavailability Studies).
c Geometric mean ratio (fed/fasted) (90% confidence interval). Moderate-fat meal = ~625 kcal, 32% fat.
d The effect of a high fat, high calorie meal on the absorption of dolutegravir and rilpivirine when administered as a fixed-dose combination tablet has not been assessed in an appropriately designed study.
e Dosing in mass balance studies: single-dose administration of [14C] dolutegravir or [14C] rilpivirine.
The JULUCA tablet taken with a moderate fat meal [approximately 625 kcal, 32% from fat] is bioequivalent to dolutegravir 50 mg and rilpivirine 25 mg tablets administered together with a meal (see 14.2 Comparative Bioavailability Studies).
Absorption: After oral administration of JULUCA with a moderate-fat meal, dolutegravir is absorbed with a median Tmax at 3 hours and rilpivirine is absorbed with a median Tmax of 4 hours (see 14.2 Comparative Bioavailability Studies).
The absolute bioavailability of dolutegravir or rilpivirine has not been established.
Effect of Food on Oral Absorption
JULUCA should be taken with a meal. When JULUCA was taken with a meal, the absorption of both dolutegravir and rilpivirine was increased. Moderate fat meals increased the dolutegravir AUC(0-∞) by approximately 87% and Cmax by approximately 75%. Rilpivirine AUC(0-∞) was increased by 57% and Cmax by 89%, compared to fasted conditions.
When administered in a single dose as TIVICAY tablets, food increases the extent and slows the rate of absorption of dolutegravir. Bioavailability of dolutegravir depends on meal content: low, moderate, and high fat meals increased dolutegravir AUC (0-∞) by 33%, 41%, and 66%, increased Cmax by 46%, 52%, and 67%, prolonged Tmax to 3, 4, and 5 hours from 2 hours under fasted conditions, respectively. These increases are not clinically significant.
When administered in a single dose as EDURANT tablets, the exposure to rilpivirine was approximately 40% lower when taken in a fasted condition as compared to a normal caloric meal (533 kcal) or high-fat high-caloric meal (928 kcal). When rilpivirine was taken with only a protein-rich nutritional drink, exposures were 50% lower than when taken with a meal. Therefore, to achieve optimal exposure, EDURANT should be taken with a meal (see 4 DOSAGE AND ADMINISTRATION)
The effect of a high fat, high calorie meal on the absorption of dolutegravir and rilpivirine when administered as a fixed-dose combination tablet has not been assessed in an appropriately designed study.
Distribution: Dolutegravir is highly bound (≥ 98.9%) to human plasma proteins based on in vivo data and binding is independent of plasma dolutegravir concentration. The apparent volume of distribution (Vd/F) following 50 mg once daily oral administration was estimated at 17.4 L based on population pharmacokinetic analysis. Rilpivirine is highly bound (approximately 99.7%) to plasma proteins in vitro, primarily to albumin.
Cerebrospinal Fluid (CSF)
In 12 treatment-naïve patients on dolutegravir plus abacavir/lamivudine, the median dolutegravir concentration in CSF was 18 ng/mL (ranging from 4 to 23 ng/mL) 2 to 6 hours post-dose after 2 weeks of treatment. The clinical relevance of this finding has not been established.
Metabolism: Dolutegravir is primarily metabolized via UGT1A1 with a minor CYP3A component (9.7% of total dose administered in a human mass balance study). Dolutegravir is the predominant circulating compound in plasma; renal elimination of unchanged drug is low (<1% of the dose).
In vitro experiments indicate that rilpivirine primarily undergoes oxidative metabolism mediated by the cytochrome P450 (CYP) 3A system.
Elimination: Dolutegravir has a terminal half-life of ~14 hours. Fifty-three percent of total oral dose is excreted unchanged in the faeces. It is unknown if all or part of this is due to unabsorbed drug or biliary excretion of the glucuronidate conjugate, which can be further degraded to form the parent compound in the gut lumen.
Rilpivirine has a terminal elimination half-life of approximately 45 hours. After single dose oral administration of 14C-rilpivirine, on average 85% and 6.1% of the radioactivity could be retrieved in feces and urine, respectively. In feces, unchanged rilpivirine accounted for on average 25% of the administered dose. Only trace amounts of unchanged rilpivirine (< 1% of total dose) were detected in urine.
Special Populations and Conditions
Pediatrics: JULUCA has not been studied in the pediatric population.
Geriatrics: Population pharmacokinetic analysis using data in HIV-1-infected adults showed that there was no clinically relevant effect of age on dolutegravir or rilpivirine exposures. Pharmacokinetic data in patients >65 years old are limited.
Sex: Population pharmacokinetic analyses revealed no clinically relevant effect of gender on the exposure of dolutegravir or rilpivirine.
Pregnancy and Breast-feeding:
Pregnancy and Postpartum
The exposure to total rilpivirine after intake of rilpivirine 25 mg once daily as part of an antiretroviral regimen was lower during pregnancy (similar for the 2nd and 3rd trimester) compared with postpartum. The decrease in unbound (active) rilpivirine pharmacokinetic parameters during pregnancy compared with postpartum was less pronounced than for total rilpivirine. In women receiving rilpivirine 25 mg once daily during the 2nd trimester of pregnancy, mean intra-individual values for total rilpivirine Cmax, AUC24h and Cmin values were 21%, 29% and 35%, respectively, lower as compared with postpartum; during the 3rd trimester of pregnancy, Cmax, AUC24h and Cmin values were 20%, 31% and 42%, respectively, lower as compared with postpartum. There are no pharmacokinetic data on the use of dolutegravir in pregnancy.
Genetic Polymorphism: In a meta-analysis using pharmacogenomics samples collected in clinical studies in healthy subjects, subjects with UGT1A1 (n=7) genotypes conferring poor dolutegravir metabolism had a 32% lower clearance of dolutegravir and 46% higher AUC compared with subjects with genotypes associated with normal metabolism via UGT1A1 (n=41). Rilpivirine pharmacokinetics are not anticipated to be impacted by polymorphisms in drug metabolising enzymes.
Ethnic origin: Population pharmacokinetic analyses of both dolutegravir and rilpivirine in HIV infected patients indicated that race had no clinically relevant effect on exposure to either dolutegravir or rilpivirine.
Hepatic Insufficiency: Dolutegravir and rilpivirine are primarily metabolized and eliminated by the liver. No dosage adjustment is necessary for patients with mild to moderate hepatic insufficiency (Child-Pugh score A or B). In a study comparing 8 patients with moderate hepatic insufficiency (Child-Pugh score B) to 8 matched healthy adult controls, the single 50 mg dose exposure of dolutegravir was similar between the two groups. In a study comparing 8 patients with mild hepatic insufficiency (Child-Pugh score A) to 8 matched controls, and 8 patients with moderate hepatic insufficiency (Child-Pugh score B) to 8 matched controls, the multiple dose exposure of rilpivirine was 47% higher in patients with mild hepatic insufficiency and 5% higher in patients with moderate hepatic insufficiency. The effect of severe hepatic insufficiency (Child-Pugh score C) on the pharmacokinetics of dolutegravir or rilpivirine have not been studied.
Renal Insufficiency: Population pharmacokinetic analyses indicated that mild and moderate renal impairment had no clinically relevant effect on the exposure of dolutegravir. Dolutegravir AUC, Cmax, and C24 were lower by 40%, 23%, and 43%, respectively, in subjects (n = 8) with severe renal impairment (creatinine clearance less than 30 mL/min) as compared with matched healthy controls. There is limited information on dolutegravir in patients requiring dialysis. Population pharmacokinetic analyses indicated that mild renal impairment had no clinically relevant effect on the exposure of rilpivirine. There is limited or no information regarding the pharmacokinetics of rilpivirine in patients with moderate or severe renal impairment, end-stage renal disease, or patients requiring dialysis.
Hepatitis B or Hepatitis C Co-infection: Population pharmacokinetic analysis indicated that hepatitis C virus co-infection had no clinically relevant effect on the exposure to dolutegravir or rilpivirine. Patients with hepatitis B co-infection were excluded from studies with JULUCA.
11 Storage, Stability, and Disposal
Store JULUCA up to 30ºC, and in the original package to protect from moisture. Keep the bottle tightly closed. Do not remove the silica gel desiccant.
Healthcare professionals should recommend that their patients return all unused medications to a pharmacy for proper disposal.
Part 2: Pharmaceutical Information
13 Pharmaceutical Information
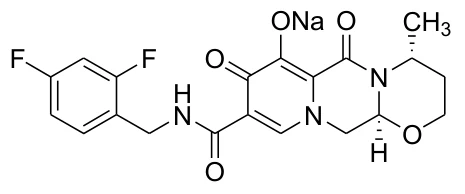
Dolutegravir
Drug Substance
Common name: dolutegravir sodium
Chemical name: sodium (4R,12aS)-9-{[(2,4-difluorophenyl)methyl]carbamoyl}-4-methyl-6,8-dioxo-3,4,6,8,12,12a-hexahydro-2H-pyrido[1',2':4,5]pyrazino[2,1-b][1,3]oxazin-7-olate
Molecular formula and molecular mass: C20H18F2N3NaO5
441.36 g/mol
Structural formula:
Physicochemical properties: Dolutegravir sodium is a white to light yellow powder and is slightly soluble in water.
Rilpivirine
Drug Substance
Common name: rilpivirine hydrochloride
Chemical name: 4-[[4-[[4-[(E)-2-cyanoethenyl]-2,6-dimethylphenyl]amino]-2- pyrimidinyl]amino]benzonitrile monohydrochloride
Molecular formula and molecular mass: C22 H18 N6 . HCl
402.88 g/mol
Structural formula:
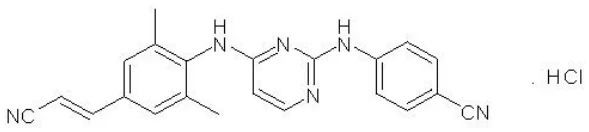
Physicochemical properties: Description: Rilpivirine hydrochloride is a white to almost white powder.
Solubility: Rilpivirine hydrochloride is practically insoluble in water over a wide pH range.
14 Clinical Trials
14.1 Clinical Trials by Indication
Treatment of human immunodeficiency virus (HIV-1) infection in adults who are virologically stable and suppressed (HIV-1 RNA less than 50 copies per mL)
Trial Design and Study Demographics
The efficacy of JULUCA is supported by data from 2 randomized, open-label, controlled trials (SWORD-1 [201636] and SWORD-2 [201637]) in virologically suppressed patients switching from their current antiretroviral regimen (CAR) to dolutegravir plus rilpivirine.
SWORD-1 and SWORD-2 are identical 148-week, Phase III, randomized, multicenter, parallel-group, non-inferiority studies. A total of 1,024 adult HIV-1-infected patients who were on a stable suppressive antiretroviral regimen (containing 2 NRTIs plus either an INSTI, an NNRTI, or a PI) received treatment in the studies. Patients were randomized 1:1 to continue their CAR or be switched to a two-drug regimen of dolutegravir plus rilpivirine administered once daily. At Week 52, patients who were initially randomized to continue their CAR and remained virologically suppressed switched to dolutegravir plus rilpivirine. The primary efficacy endpoint for the SWORD studies was the proportion of patients virologically suppressed defined as plasma HIV-1 RNA less than 50 copies per mL at Week 48 (Snapshot algorithm for the ITT-E population).
In the pooled analysis, 54%, 26%, and 20% of patients were receiving an NNRTI, PI, or INSTI (respectively) as their baseline core agent class prior to randomization. The demographic baseline characteristics and core agent class were similarly distributed between treatment arms (see Table 10).
Table 10 Summary of Baseline Characteristics for Studies SWORD-1 (201636), SWORD-2 (201637), and Pooled Data (ITT-E Population)
| SWORD-1 | SWORD-2 | POOLED | |||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| DTG + RPV | CAR | DTG + RPV | CAR | DTG + RPV | CAR | ||||||||||||||||||
| N=252 (%) | N=256 (%) | N=261 (%) | N=255 (%) | N=513 (%) | N=511 (%) | ||||||||||||||||||
| Baseline HIV-1 RNA (c/mL) | |||||||||||||||||||||||
| <50 c/mL | 247(98) | 253 (99) | 259 (99) | 251 (98) | 506 (99) | 504 (99) | |||||||||||||||||
| ≥50 c/mL | 5 (2) | 3 (1) | 2 (1) | 4 (2) | 7 (1) | 7 (1) | |||||||||||||||||
| Baseline CD4+ (log10 cells/mm3) | |||||||||||||||||||||||
| Median | 2.786 | 2.805 | 2.785 | 2.798 | 2.786 | 2.805 | |||||||||||||||||
| Min., Max. | 1.57, 3.18 | 1.98, 3.18 | 2.06, 3.25 | 2.03, 3.22 | 1.57, 3.25 | 1.98, 3.22 | |||||||||||||||||
| Age (y) median (range) | 43.0 (23-78) | 43.0 (22-76) | 43.0 (21-79) | 43.0 (22-69) | 43.0 (21-79) | 43.0 (22-76) | |||||||||||||||||
| Sex | |||||||||||||||||||||||
| Female | 58 (23) | 51(20) | 62 (24) | 57 (22) | 120 (23) | 108 (21) | |||||||||||||||||
| Male | 194 (77) | 205 (80) | 199 (76) | 198 (78) | 393 (77) | 403 (79) | |||||||||||||||||
| Race, n(%) | |||||||||||||||||||||||
| American Indian or Alaska Native | 3 (1) | 6 (2) | 11 (4) | 8 (3) | 14 (3) | 14 (3) | |||||||||||||||||
| Asian | 25 (10) | 34 (13) | 13 (5) | 16 (6) | 38 (7) | 50 (1) | |||||||||||||||||
| Black/African American | 24 (10) | 27 (11) | 13 (5) | 20 (8) | 37 (7) | 47 (9) | |||||||||||||||||
| White | 198 (79) | 188 (73) | 223 (85) | 210 (82) | 421 (82) | 398 (78) | |||||||||||||||||
| Hepatitis B & C Test Results | |||||||||||||||||||||||
| C only | 15 (6) | 19 (7) | 13 (5) | 21 (8) | 28 (5) | 40 (8) | |||||||||||||||||
| CDC Category | |||||||||||||||||||||||
| A: | 203 (81) | 198 (77) | 197 (75) | 187 (73) | 400 (78) | 385 (75) | |||||||||||||||||
| B: | 20 (8) | 35 (14) | 35 (13) | 33 (13) | 55 (11) | 68 (13) | |||||||||||||||||
| C: | 29 (12%) | 23 (9%) | 29 (11%) | 34 (13%) | 58 (11%) | 57 (11%) | |||||||||||||||||
Study Results
The pooled primary analysis demonstrated that dolutegravir plus rilpivirine is non-inferior to CAR, with 95% of patients in both arms achieving the primary endpoint of <50 copies/mL plasma HIV-1 RNA at Week 48 based on the Snapshot algorithm [ITT-E Population (Table 11)].
The primary endpoint and other outcomes (including outcomes by key baseline covariates) for the pooled SWORD-1 and SWORD-2 studies are shown in Table 11.
Table 11 Virologic Outcomes of Randomized Treatment at Week 48 (Snapshot Algorithm, ITT-E Population)
SWORD-1 and SWORD-2 Pooled Data | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Dolutegravir plus Rilpivirine (N=513) n (%) | Current Antiretroviral Regimen (N=511) n (%) | ||||||||||||
| HIV-1 RNA <50 copies/mL | (486/513) 95% | (485/511) 95% | |||||||||||
| Treatment Difference* | -0.2% (95% CI: -3.0%, 2.5%) | ||||||||||||
| Virologic non response† | 3 (<1%) | 6 (1%) | |||||||||||
| Reasons | |||||||||||||
| Data in window not <50 copies/mL | 0 | 2 (<1%) | |||||||||||
| Discontinued for lack of efficacy | 2 (<1%) | 2 (<1%) | |||||||||||
| Discontinued for other reasons while not <50 copies/mL | 1 (<1%) | 1 (<1%) | |||||||||||
| Change in (ART) | 0 | 1 (<1%) | |||||||||||
| No virologic data at Week 48 window | 24 (5%) | 20 (4%) | |||||||||||
| Reasons | |||||||||||||
| Discontinued study/study drug due to adverse event or death | 17 (3%) | 3 (<1%) | |||||||||||
| Discontinued study/study drug for other reasons** | 7 (1%) | 16 (3%) | |||||||||||
| Missing data during window but on study | 0 | 1 (<1%) | |||||||||||
| HIV-1 RNA <50 copies/mL by baseline covariates | |||||||||||||
| n/N (%) | n/N (%) | ||||||||||||
| Baseline CD4+ (cells/ mm3) | |||||||||||||
| <350 | 51 / 58 (88%) | 46 / 52 (88%) | |||||||||||
| ≥350 | 435 / 455 (96%) | 439 / 459 (96%) | |||||||||||
| Baseline Core Agent Class | |||||||||||||
| INSTI | 99 / 105 (94%) | 92 / 97 (95%) | |||||||||||
| NNRTI | 263 / 275 (96%) | 265 / 278 (95%) | |||||||||||
| PI | 124 / 133 (93%) | 128 / 136 (94%) | |||||||||||
| Gender | |||||||||||||
| Male | 375 / 393 (95%) | 387 / 403 (96%) | |||||||||||
| Female | 111 / 120 (93%) | 98 / 108 (91%) | |||||||||||
| Race | |||||||||||||
| White | 395 / 421 (94%) | 380 / 400 (95%) | |||||||||||
| African-America/African Heritage/Other | 91/92 (99%) | 105 / 111 (95%) | |||||||||||
| Age (years) | |||||||||||||
| <50 | 350 / 366 (96%) | 348 / 369 (94%) | |||||||||||
| ≥50 | 136 / 147 (93%) | 137 / 142 (96%) | |||||||||||
Treatment difference [(dolutegravir plus rilpivirine)–current antiretroviral regimen] Adjusted for baseline stratification factors and assessed using a non-inferiority margin of -8% (Intent-to-Treat Exposed population)
† Non-inferiority of DTG + RPV to CAR in the proportion of patients classified as virologic non-responders was demonstrated using a non-inferiority margin of 4%. Adjusted difference (95% CI) -0.6 (-1.7, 0.6)
**Other includes reasons such as withdrew consent, loss to follow-up, moved, and protocol deviation
All subgroup results (i.e. CD4+ cell count, age, gender, race, and baseline core agent class) were consistent with the primary analysis.
At Week 148 in the pooled SWORD-1 and SWORD-2 trials, 84% of subjects who received dolutegravir plus rilpivirine from study start had plasma HIV-1 RNA < 50 copies/mL based on the Snapshot algorithm. In subjects who initially remained on their CAR and switched to dolutegravir plus rilpivirine at Week 52, 90% had plasma HIV-1 RNA < 50 copies/mL at Week 148 based on the Snapshot algorithm, which was comparable to the response rate (89%) observed at Week 100 (similar exposure duration) in subjects receiving dolutegravir plus rilpivirine from study start.
14.2 Comparative Bioavailability Studies
A single-dose, 2-period, randomized, open-label, crossover study was conducted to evaluate the pivotal bioequivalence of an oral 1 x JULUCA (50 mg dolutegravir/25 mg rilpivirine) fixed dose combination tablet compared with co-administration of the separate tablet formulations of a 1 x TIVICAY (dolutegravir 50 mg) tablet and a 1 x EDURANT (rilpivirine 25 mg) tablet under moderate-fat fed conditions ([~625 kcal: 125 kcal from protein (20%), 300 kcal from carbohydrate (48%), and 200 kcal from fat (32%)]). The study was conducted in healthy, adult male and female subjects (n=118).
TIVICAY (50 mg dolutegravir) tablets and EDURANT (25 mg rilpivirine) tablets administered as reference products in the study are comparable to the commercial marketed products.
The JULUCA (50 mg dolutegravir/25 mg rilpivirine) fixed dose combination tablet was bioequivalent to TIVICAY (dolutegravir 50 mg) tablets plus EDURANT (rilpivirine 25 mg) tablets co-administered as separate tablets after a moderate-fat meal. The results from 113 subjects are presented below.
Table 12 Summary of the Comparative Bioavailability Data for Dolutegravir
Dolutegravir (1 x 50 mg) MODERATE-FAT FED CONDITIONS From measured data Geometric Mean5 Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | Ratio of Geometric Means in % | 90% Confidence Interval |
AUCT (ng.h/mL) | 63583.4 65510.8 (24) | 61265.4 63225.3 (26) | 103.8 | (101.1, 106.6) |
AUCI (ng.h/mL) | 64967.8 66881.9 (24) | 62654.9 64606.8 (25) | 103.7 | (101.0, 106.4) |
CMAX (ng/mL) | 3646.0 3703.3 (17) | 3473.9 3534.4 (19) | 105.0 | (102.2, 107.8) |
TMAX3 (h) | 3.0 (0.5, 6.0) | 3.0 (0.5, 8.0) | ||
| T½4 (h) | 14.8 (21) | 15.1 (21) | ||
1 JULUCA (50 mg dolutegravir/25 mg rilpivirine) fixed-dose combination tablets
2 TIVICAY (50 mg dolutegravir) and EDURANT (25 mg rilpivirine) tablets administered concurrently
3 Expressed as median (range)
4 Expressed as the arithmetic mean (CV%) only
5 Adjusted geometric mean
Table 13 Summary of the Comparative Bioavailability Data for Rilpivirine
Rilpivirine (1 x 25 mg) MODERATE-FAT FED CONDITIONS From measured data Geometric Mean7 Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | Ratio of Geometric Means in % | 90% Confidence Interval |
AUC0-72 (ng.h/mL) | 2016.6 2125.7 (31) | 1834.8 1948.9 (35) | 109.9 | (103.7, 116.5) |
AUCI (ng.h/mL) | 3248.05 | 2932.55 | 110.8 | (104.5, 117.4) |
3254.46 3521.1 (40) | 2936.06 3183.8 (41) | 110.8 | (104.6, 117.5) | |
CMAX (ng/mL) | 93.3 100.1 (34) | 83.0 88.4 (34) | 112.4 | (104.7, 120.7) |
TMAX3 (h) | 4.0 (1.0, 9.0) | 4.0 (1.5, 9.0) | ||
| T½4 (h) | 55.8 (39) | 56.9 (44) | ||
1 JULUCA (50 mg dolutegravir/25 mg rilpivirine) fixed-dose combination tablets.
2 TIVICAY (50 mg dolutegravir) and EDURANT (25 mg rilpivirine) tablets administered concurrently.
3 Expressed as median (range)
4 Expressed as the arithmetic mean (CV%) only.
5 For AUCI, 1 subject was excluded from both periods due to a result “not determined” in reference treatment; in a separate supportive analysis this subject’s test treatment AUC (0-∞) was included
6 Adjusted geometric mean
15 Microbiology
Antiviral Activity in cell culture
Dolutegravir exhibited antiviral activity against laboratory strains of wild-type HIV-1 with mean EC50 values of 0.51 nM to 2.1 nM in peripheral blood mononuclear cells (PBMCs) and MT-4 cells.
When dolutegravir was tested in PBMC assays against a panel consisting of 24 HIV-1 clinical isolates [group M (clades A, B, C, D, E, F and G) and group O] and 3 HIV-2 clinical isolates, the geometric mean EC50 was 0.20 nM (0.02 to 2.14 nM) for HIV-1, while the geometric mean EC50 was 0.18 nM (0.09 to 0.61nM) for HIV-2 isolates.
Rilpivirine exhibited activity against laboratory strains of wild-type HIV-1 in an acutely infected T-cell line with a median EC50 value for HIV-1/IIIB of 0.73 nM (0.27 ng/mL).
Rilpivirine also demonstrated antiviral activity against a broad panel of HIV-1 group M (clade A, B, C, D, F, G, H) primary isolates with median EC50 values ranging from 0.07 to 1.01 nM and group O primary isolates with EC50 values ranging from 2.88 to 8.45 nM.
Antiviral Activity in combination with other antiviral agents
The following drugs were not antagonistic with dolutegravir in in vitro assessments conducted in checkerboard format: stavudine, abacavir, efavirenz, nevirapine, lopinavir, amprenavir, enfuvirtide, maraviroc, adefovir and raltegravir. In addition, the anti-HCV drug ribavirin had no apparent effect on dolutegravir activity.
No drugs with inherent anti-HIV activity were antagonistic with rilpivirine (abacavir, amprenavir, atazanavir, darunavir, didanosine, efavirenz, emtricitabine, enfuvirtide, etravirine, indinavir, lamivudine, lopinavir, maraviroc, nelfinavir, nevirapine, raltegravir, ritonavir, saquinavir, stavudine, tenofovir, tipranavir, and zidovudine).
The combination of dolutegravir plus rilpivirine evaluated in an in vitro two-drug combination study showed no antagonistic interactions.
Effect of Human Serum and Serum Proteins
In vitro studies suggested a 75-fold shift in EC50 of dolutegravir in the presence of 100% human serum (by method of extrapolation), and the protein adjusted EC90 (PA-EC90) in PBMCs was estimated to be 0.064 μg/mL. Dolutegravir trough concentration for a single 50 mg dose in integrase inhibitor naïve patients was 1.20 μg/mL, 19 times higher than the estimated PA-EC90.
Resistance in vitro
Isolation from wild type HIV-1 and activity against resistant strains: Viruses highly resistant to dolutegravir were not observed during the 112 day passage of strain IIIB, with a 4.1-fold maximum fold change (FC) observed for the passaged resistant virus populations with amino acid substitutions at the conserved IN positions S153Y and S153F. Passage of the wild type HIV-1 strain NL432 in the presence of dolutegravir selected for E92Q (passage population virus FC=3.1) and G193E (passage population virus FC=3.2) substitutions on Day 56. Additional passage of wild type clade B, C, and A/G viruses in the presence of dolutegravir selected for R263K, G118R, and S153T.
Rilpivirine-resistant strains were selected in cell culture starting from wild type HIV-1 of different origins and clades as well as NNRTI-resistant HIV-1. The most commonly observed amino acid substitutions that emerged included: L100I, K101E, V108I, E138K, V179F, Y181C, H221Y, F227C and M230I. Resistance to rilpivirine was considered present when FC in EC50 value was above the biological cut-off (BCO) of the assay.
Resistance in vivo
Overall, 11 subjects receiving dolutegravir plus rilpivirine in the pooled SWORD-1 and SWORD-2 trials had confirmed virologic failure through Week 148.
Through Week 48 with comparative data, two subjects receiving dolutegravir plus rilpivirine and two subjects continuing their current antiretroviral regimen had confirmed virologic failure. The 2 subjects in the dolutegravir/rilpivirine arm had detectable resistance substitutions at rebound. One subject had the NNRTI-resistance-associated substitution K101K/E with no decreased susceptibility to rilpivirine (FC = 0.75) at Week 36, had no INSTI resistance-associated substitutions or decreased susceptibility to dolutegravir (FC less than 2), and had HIV-1 RNA less than 50 copies per mL at the withdrawal visit. The other subject had the dolutegravir resistance-associated substitution G193E at baseline (by exploratory HIV proviral DNA archive sequencing) and Week 24 (by conventional sequencing) without decreased susceptibility to dolutegravir (FC= 1.02) at Week 24. No resistance-associated substitutions were observed for the other 2 subjects in the comparative current antiretroviral regimen arms.
From Week 48 through Week 148, in the pooled analyses, 9 additional subjects receiving dolutegravir plus rilpivirine had confirmed virologic failure at any time. Eight of the 9 subjects had resistance testing results available; 6 of the 8 subjects had postbaseline results and NNRTI resistance-associated substitutions at virologic failure. These 6 subjects are further described below.
Four Subjects Receiving Dolutegravir plus Rilpivirine from Study Start: At Week 88, one subject had the NNRTI resistance-associated substitution mixture E138E/A with no decreased susceptibility to rilpivirine (FC= 1.6), and a second subject had K103N with rilpivirine FC= 5.2. Neither subject had INSTI resistance-associated substitutions or decreased susceptibility to dolutegravir. At Week 100, a third subject with baseline NNRTI resistance-associated substitutions K101E and E138A had M230M/L in addition to K101E and E138A with rilpivirine FC = 31. Integrase resistance testing failed at virologic failure. At Week 112, a fourth subject had M230M/L mixture with rilpivirine FC= 2 and had INSTI polymorphic substitutions E157Q, G193E, and T97T/A at baseline; at virologic failure E157Q and G193E were still present, while T97T/A was no longer observed and there was no decreased susceptibility to dolutegravir (FC= 1.5).
Two Subjects Receiving Dolutegravir plus Rilpivirine from Week 52: At Week 64, one subject had integrase substitutions N155H and G163G/R at baseline and only polymorphic integrase V151I/V mixture at virologic failure, and no NNRTI resistance. Integrase phenotype assay failed for this subject, and HIV-1 RNA was less than 50 copies per mL at the withdrawal visit. At Week 136, a second subject had NNRTI resistance-associated substitutions E138A and L100L/I with rilpivirine FC= 4.1, and integrase resistance testing failed at virologic failure.
Treatment-naïve HIV-1-infected patients on Dolutegravir: Please refer to the TIVICAY product monograph.
Treatment-naïve HIV-1-infected patients on Rilpivirine: Please refer to the EDURANT product monograph.
Cross-resistance
Site-directed INSTI mutant virus: Dolutegravir activity was determined against a panel of 60 INSTI-resistant site-directed mutant HIV-1 viruses (28 with single substitutions and 32 with 2 or more substitutions). The single INSTI-resistance substitutions T66K, I151L, and S153Y conferred a greater than 2-fold decrease in dolutegravir susceptibility (range: 2.3-fold to 3.6-fold from reference). Combinations of multiple substitutions T66K/L74M, E92Q/N155H, G140C/Q148R, G140S/Q148H, R or K, Q148R/N155H, T97A/G140S/Q148, and substitutions at E138/G140/Q148 showed a greater than 2-fold decrease in dolutegravir susceptibility (range: 2.5-fold to 21-fold from reference).
Site-directed NNRTI mutant virus: In a panel of 67 HIV-1 recombinant laboratory strains with one amino acid substitution at RT positions associated with NNRTI resistance, including the most commonly found K103N and Y181C, rilpivirine showed antiviral activity (FC<BCO) against 64 (96%) of these strains. The single amino acid substitutions associated with a loss of susceptibility to rilpivirine were: K101P, Y181I and Y181V. The K103N substitution did not result in reduced susceptibility to rilpivirine by itself, but the combination of K103N and L100I resulted in a 7-fold reduced susceptibility to rilpivirine.
Considering all of the available in vitro and in vivo data, the following amino acid substitutions, when present at baseline, are likely to affect the activity of rilpivirine: K101E, K101P, E138A, E138G, E138K, E138R, E138Q, V179L, Y181C, Y181I, Y181V, Y188L, H221Y, F227C, M230I, or M230L.
Cross-resistance to efavirenz, etravirine, and/or nevirapine is likely after virologic failure and development of rilpivirine resistance.
Recombinant Resistant clinical isolates: Dolutegravir activity was measured for 705 raltegravir resistant recombinant isolates from clinical practice; 93.9% (662/705) of the isolates had a dolutegravir FC ≤10 and 1.8% had a DTG FC > 25. Mutants with Y143 and N155 pathway had mean FCs of 1.2 and 1.5, respectively, while Q148 + 1 mutant and Q148 + ≥ 2 mutants mean FCs were 4.8 and 6.0, respectively.
Rilpivirine retained sensitivity (FC ≤ BCO) against 62% of 4786 HIV-1 recombinant clinical isolates resistant to efavirenz and/or nevirapine.
16 Non-Clinical Toxicology
General Toxicology
The effect of prolonged daily treatment with high doses of dolutegravir has been evaluated in repeat oral dose toxicity studies in rats (up to 26 weeks) and in monkeys (up to 38 weeks). The primary effect of dolutegravir was gastrointestinal intolerance or irritation in rats and monkeys at doses that produce systemic exposures approximately 30 and 1.2 times the 50 mg human clinical exposure based on AUC, respectively. Because gastrointestinal (GI) intolerance is considered to be due to local drug administration, mg/kg or mg/m2 metrics are appropriate determinates of safety cover for this toxicity. GI intolerance in monkeys occurred at 30 times the human mg/kg equivalent dose (based on 50 kg human), and 11 times the human mg/m2 equivalent dose for a total daily clinical dose of 50 mg.
Animal toxicology studies have been conducted with rilpivirine in mice, rats, rabbits, dogs and cynomolgus monkeys. The target organs and systems of toxicity were the adrenal cortex and the associated steroid biosynthesis (mouse, rat, dog, cynomolgus monkey), the reproductive organs (female mouse, male and female dog), the liver (mouse, rat, dog), the thyroid and pituitary gland (rat), the kidney (mouse, dog), the hematopoietic system (mouse, rat, dog), and the coagulation system (rat).
Carcinogenesis/mutagenesis
Dolutegravir was not mutagenic or clastogenic using in vitro tests in bacteria and cultured mammalian cells, and an in vivo rodent micronucleus assay. Dolutegravir was not carcinogenic in long term studies in the mouse and rat.
Rilpivirine was evaluated for carcinogenic potential by oral gavage administration to mice and rats up to 104 weeks. Daily doses of 20, 60 and 160 mg/kg/day were administered to mice and doses of 40, 200, 500 and 1,500 mg/kg/day were administered to rats. An increase in the incidences of hepatocellular adenomas and carcinomas was observed in mice and rats. An increase in the incidences of follicular cell adenomas and/or carcinomas in the thyroid gland was observed in rats. Administration of rilpivirine did not cause a statistically significant increase in the incidence of any other benign or malignant neoplasm in mice or rats. The observed hepatocellular findings in mice and rats are considered to be rodent-specific, associated with liver enzyme induction. A similar mechanism does not exist in humans; hence, these tumours are not relevant for humans. The follicular cell findings are considered to be rat-specific associated with increased clearance of thyroxine and are not considered to be relevant for humans. At the lowest tested doses in the carcinogenicity studies, the systemic exposures (based on AUC) to rilpivirine were 21-fold (mice) and 3-fold (rats), relative to those observed in humans at the recommended dose (25 mg once daily).
Rilpivirine has tested negative in the in vitro Ames reverse mutation assay and in vitro clastogenicity mouse lymphoma assay, tested in the absence and presence of a metabolic activation system. Rilpivirine did not induce chromosomal damage in the in vivo micronucleus test in mice.
Reproductive and Developmental Toxicology
Pregnancy
Oral administration of dolutegravir to pregnant rats at doses up to 1,000 mg/kg daily from days 6 to 17 of gestation did not elicit maternal toxicity, developmental toxicity or teratogenicity (37.9 times the 50 mg human clinical exposure based on AUC).
Oral administration of dolutegravir to pregnant rabbits at doses up to 1000 mg/kg daily from days 6 to 18 of gestation did not elicit developmental toxicity or teratogenicity (0.56 times the 50 mg human clinical exposure based on AUC). In rabbits, maternal toxicity (decreased food consumption, scant/no faeces/urine, suppressed body weight gain) was observed at 1,000 mg/kg (0.56 times the 50 mg human clinical exposure based on AUC). In a non-clinical distribution study in animals, dolutegravir was shown to cross the placenta.
Studies in animals have shown no evidence of relevant embryonic or fetal toxicity or an effect on reproductive function with rilpivirine. There was no teratogenicity with rilpivirine in rats and rabbits. The exposures at the embryo-fetal No Observed Adverse Effects Levels (NOAELs) in rats and rabbits were respectively 15 and 70 times higher than the exposure in humans at the recommended dose of 25 mg once daily. In a pre- and postnatal development assessment in rats, rilpivirine had no effect on development of offspring during lactation or post weaning when the mothers were dosed up to 400 mg/kg/day.
Fertility
Dolutegravir did not affect male or female fertility in rats at doses up to 1,000 mg/kg/day, the highest dose tested (33 times the 50 mg human clinical exposure based on AUC).
In rats, there were no effects on mating or fertility with rilpivirine up to 400 mg/kg/day, a dose that showed maternal toxicity. This dose is associated with an exposure that is approximately 40 times higher than the exposure in humans at the recommended dose of 25 mg once daily.
17 Supporting Product Monographs
- 1. EDURANT (tablets, 25 mg rilpivirine), submission control #185031, Product Monograph, Janssen Inc. (May 10, 2016)
- 2. TIVICAY (tablets, 10, 25, and 50 mg dolutegravir), submission control #192462, Product Monograph, ViiV Healthcare ULC. (Feb., 03, 2017).