


Product Monograph - Lantus (Sanofi-Aventis Canada, PM 00034372)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Subcutaneous | Solution for injection 100 U/mL | glycerol 85%, m-cresol, polysorbate 20 (10 mL vial only), zinc, and water for injection. Hydrochloric acid and sodium hydroxide for pH adjustment. |
DESCRIPTION
LANTUS [insulin glargine injection (rDNA origin)] is a recombinant human insulin analogue that is a long-acting, parenteral blood-glucose-lowering agent. LANTUS is produced by recombinant DNA technology utilizing a non-pathogenic laboratory strain of Escherichia coli (K12) as the production organism.
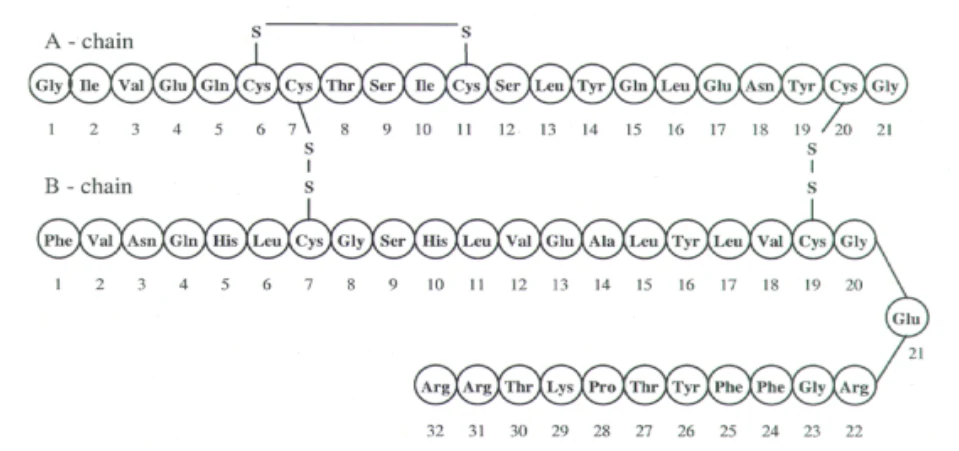
Insulin glargine differs from natural human insulin in that the amino acid asparagine at position 21 of the A-chain is replaced by glycine and two arginines are added to the C-terminus of the B-chain (see PHARMACEUTICAL INFORMATION, Drug Substance).
INDICATIONS AND CLINICAL USE
LANTUS [insulin glargine injection (rDNA origin)] is a recombinant human insulin analog indicated for once-daily subcutaneous administration in the treatment of patients over 17 years of age with Type 1 or Type 2 diabetes mellitus who require basal (long-acting) insulin for the control of hyperglycemia.
LANTUS is also indicated in the treatment of pediatric patients (˃6 years old) with Type 1 diabetes mellitus who require basal (long-acting) insulin for the control of hyperglycemia.
CONTRAINDICATIONS
LANTUS [insulin glargine injection (rDNA origin)] is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions Hypoglycemia is the most common adverse effect of insulin, including LANTUS (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypoglycemia). As with all insulins, the timing of hypoglycemia may differ among various insulin formulations. Glucose monitoring is recommended for all patients with diabetes. Uncorrected hypoglycemic or hyperglycemic reactions can cause loss of consciousness, coma, or death. Any change of insulin should be made cautiously and only under medical supervision. LANTUS is not intended for intravenous or intramuscular administration. The prolonged duration of activity of insulin glargine is dependent on injection into subcutaneous tissue. Intravenous administration of the usual subcutaneous dose could result in severe hypoglycemia. LANTUS must not be mixed with any other insulin or diluted with any other solution. If LANTUS is diluted or mixed, the solution may become cloudy, and the pharmacokinetic/ pharmacodynamic profile (e.g., onset of action, time to peak effect) of LANTUS and/or the mixed insulin may be altered in an unpredictable manner (see DOSAGE AND ADMINISTRATION). This insulin product shall not be used if it is not water-clear and colourless or if it has formed a deposit of solid particles on the wall of the vial or cartridge (see DOSAGE AND ADMINISTRATION). |
General
As with all insulin preparations, the time course of LANTUS action may vary in different individuals or at different times in the same individual and the rate of absorption is dependent on blood supply, temperature, and physical activity.
Hypokalemia is among the potential clinical adverse effect associated with the use of all insulin therapies, particularly when given intravenously. However, LANTUS should not be given intravenously (see DOSAGE AND ADMINISTRATION, Administration). If left untreated, hypokalemia may cause respiratory paralysis, ventricular arrhythmia, and death. This potential clinical adverse effect may be more relevant in patients who are at risk for hypokalemia (e.g., patient using potassium lowering drugs), patients taking medications sensitive to serum potassium concentrations, or patients losing potassium through other means (e.g. diarrhea).
Stress or concomitant illness, especially infectious and febrile conditions may change insulin requirements.
Insulin may cause sodium retention and edema, particularly if previously poor metabolic control is improved by intensified insulin therapy.
Patients with human insulin antibodies may be hypersensitive to other insulins, with a risk of hypoglycemia and/or cross-reactivity.
Thiazolidinediones (TZDs), alone or in combination with other antidiabetic agents (including insulin), can cause heart failure and edema. The combination of TZD with insulin is not indicated for the treatment of Type 2 Diabetes Mellitus. Please refer to the respective TZD product monograph WARNINGS AND PRECAUTIONS information when the use of these drugs in combination with any insulin, including LANTUS, is contemplated.
To avoid transmission of disease, cartridge or a prefilled syringe shall not be used by more than one person.
Accidental mix-ups between insulin glargine and other insulins, particularly short-acting insulins, have been reported. To avoid medication errors between insulin glargine and other insulins, patients should be instructed to always check the insulin label before each injection (see ADVERSE REACTIONS).
Endocrine and Metabolism
Hypoglycemia:
As with all insulin preparations, hypoglycemic reactions, especially during initiation of therapy, may be associated with the administration of LANTUS. Hypoglycemia is the most common adverse effect of insulins (see ADVERSE REACTIONS). Hypoglycemia may occur if the insulin dose is too high in relation to the insulin requirement (see OVERDOSAGE). Early warning symptoms of hypoglycemia may be different, be less pronounced or absent under certain conditions, as for example, in patients whose glycemic control is markedly improved, in elderly patients, in patients where an autonomic neuropathy is present, in patients whose hypoglycemia is developing gradually, in patients with a long history of diabetes, in patients with psychiatric illness, or in patients receiving concurrent treatment with certain other drugs such as beta-blockers. Hypoglycemia may occur with other substances including alcohol and psychiatric medications, street drugs, birth control pills, injections and patches (see DRUG INTERACTIONS: Drug-Drug Interactions).
Such situations may result in severe hypoglycemia (and possibly, loss of consciousness) prior to patients’ awareness of hypoglycemia.
The time of occurrence of hypoglycemia depends on the action profile of the insulins used and may, therefore, change when the treatment regimen or timing of administration is changed.
As with all insulins, prolonged or severe hypoglycemic attacks, especially if recurrent, may lead to neurological damage, loss of consciousness, coma or death (see ADVERSE REACTIONS).
As with all insulins, additional caution (including intensified blood glucose monitoring) should be exercised in patient populations who are at greater risk for clinically significant sequelae from hypoglycemic episodes.
In a clinical study, symptoms of hypoglycemia or counter regulatory hormone responses were similar after intravenous insulin glargine and regular human insulin both in healthy subjects and adult patients with type 1 diabetes.
Hypoglycemic reactions following treatment with insulin products such as LANTUS are mostly mild and easily managed. Changes in insulin therapy or changes in life style (i.e. diet, omission of a meal, exercise/ physical activity) may require a change in dosage to avoid hypoglycemia. Glucose monitoring is recommended for all patients with diabetes.
Diabetic patients should be instructed to carry a few lumps of sugar, candies or biscuits to prevent the progression of a hypoglycemic reaction, should one occur (see PART III: CONSUMER INFORMATION).
Hyperglycemia:
The use of too low insulin dosages or discontinuation of treatment, especially in Type 1 diabetes, may lead to hyperglycemia and diabetic ketoacidosis. Uncorrected hyperglycemic reactions can cause loss of consciousness, coma, or death.
Immune
Injection Site and Local Allergic Reactions:
As with any insulin therapy, lipodystrophy may occur at the injection site and delay insulin absorption. Other injection site reactions with insulin therapy include redness, pain, itching at the injection site, hives, swelling, and inflammation. Continuous rotation of the injection site within a given area may help to reduce or prevent these reactions. Most minor reactions to insulins usually resolve in a few days to a few weeks. They may occur if the injection is not properly made (irritants in the skin cleansing agent or poor injection technique), or if the patient is allergic to the insulin or any excipients.
Rarely, SC administration of insulin products can result in lipoatrophy (depression in the skin) or lipohypertrophy (enlargement or thickening of tissue). Patients should be advised to consult their doctor if they notice any of these conditions.
Reports of injection site pain were more frequent with LANTUS than NPH human insulin (2.7% insulin glargine versus 0.7% human NPH). The reports of pain at the injection site were usually mild and did not result in discontinuation of therapy. Other possibly related treatment-emergent injection site reactions occurred at similar incidences with both insulin glargine and NPH human insulin.
Systemic allergic reactions:
Immediate-type allergic reactions are rare. Such reactions to insulin (including insulin glargine) or the excipients may, for example, be associated with generalized skin reactions, angioedema, bronchospasm, hypotension, anaphylactic reaction or shock and may be life threatening (see CONTRAINDICATIONS and ADVERSE REACTIONS).
Antibody Production:
Insulin administration may cause insulin antibodies to form. In clinical studies, antibodies that cross-react with human insulin and insulin glargine were observed in both NPH human insulin and insulin glargine treatment groups with similar percents of increased and decreased titers. There was no correlation in either treatment group between increases or decreases in these antibody titers and changes in either A1C or total insulin requirements. In theory, the presence of such insulin antibodies may necessitate adjustment of the insulin dose in order to correct a tendency to hyperglycemia or hypoglycemia, but has not been found on review of LANTUS clinical trials and available post-marketing data.
Intercurrent conditions:
Insulin requirements may be altered during intercurrent conditions such as infection or illness, emotional disturbances, or stress.
Renal / Hepatic / Biliary / Pancreatic impairment
Although studies have not been performed in patients with diabetes and hepatic or renal impairment, LANTUS requirements may be diminished due to reduced capacity for gluconeogenesis and reduced insulin metabolism (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions). Careful glucose monitoring and dose adjustments of insulin or insulin analogues including LANTUS may be necessary in patients with hepatic or renal dysfunction.
Retinopathy
A marked change in glycemic control may cause temporary visual impairment, due to temporary alteration in the turgidity and refractive index of the lens.
Long-term improved glycemic control decreases the risk of progression of diabetic retinopathy. However, as for all insulin regimens, intensification of insulin therapy with abrupt improvement in glycemic control may be associated with temporary worsening of diabetic retinopathy.
In patients with proliferative retinopathy, particularly if not treated with photocoagulation, severe hypoglycemic episodes may result in transient amaurosis (see ADVERSE REACTIONS, Eye disorders).
Transferring Patients from Other Insulins
Any change of insulin should be made cautiously and only under medical supervision. Changes in insulin strength, timing of administration, manufacturer, type (e.g., regular, NPH, or insulin analogs), species (animal, human), or method of manufacture (recombinant DNA versus animal-source insulin) may result in the need for a change in dosage. Concomitant oral antidiabetic treatment may need to be adjusted. As with all insulins, when transferring to LANTUS, the early warning symptoms of hypoglycemia may be changed, be less pronounced, or absent. The prolonged effect of subcutaneous LANTUS may delay recovery from hypoglycemia (see DOSAGE AND ADMINISTRATION).
Special Populations
Pregnant Women:
Teratogenic effects
For insulin glargine no clinical data on exposed pregnancies from controlled clinical studies are available. Post Marketing data on pregnant women (more than 1000 pregnancy outcomes) indicate no reports of specific adverse effects of insulin glargine on maternal and fetal/neonatal outcomes.
Animal data do not indicate reproductive toxicity (see Part II: TOXICOLOGY, Reproduction Toxicity and Impairment of Fertility).
It is essential for patients with diabetes or a history of gestational diabetes to maintain good metabolic control throughout pregnancy to prevent adverse outcomes associated with hyperglycemia.
Insulin requirements may decrease during the first trimester and generally increase during the second and third trimesters. Immediately after delivery, insulin requirements decline rapidly (increased risk of hypoglycemia). Careful monitoring of glucose control is essential.
Patients with diabetes should be advised to inform their doctor if they are pregnant or are contemplating pregnancy.
Nursing Women:
It is unknown whether insulin glargine is excreted in significant amounts in human milk. Many drugs, including human insulin, are excreted in human milk. There are no adequate and well-controlled studies in nursing women. For this reason, caution should be exercised when LANTUS is administered to a nursing woman. Lactating women may require adjustments in insulin dose and diet.
Pediatrics (> 6 years of age):
Safety and effectiveness of LANTUS has been established in children over 6 years of age with Type 1 diabetes mellitus (see ACTIONS AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, and INDICATIONS AND CLINICAL USE).
Geriatrics (> 65 years of age):
In controlled clinical studies comparing insulin glargine to NPH human insulin, 593 of 3890 patients with type 1 and type 2 diabetes were 65 years and older. The only difference in safety or effectiveness in this subpopulation compared to the entire study population was an expected higher incidence of cardiovascular events in both insulin glargine and NPH human insulin treated patients.
In elderly patients with diabetes, the initial dosing, dose increments, and maintenance dosage should be conservative to avoid hypoglycemic reactions.
Hypoglycemia may be difficult to recognize in the elderly (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypoglycemia). In the elderly, progressive deterioration of renal function may lead to steady decrease in insulin requirements. Careful glucose monitoring and dose adjustments of insulin or insulin analogues including LANTUS may be necessary (see WARNINGS AND PRECAUTIONS, Renal/ Hepatic/ Biliary/ Pancreatic impairment).
Other:
The presence of diseases such as Acromegaly, Cushing's Syndrome, Hyperthyroidism, and Pheochromocytoma can complicate the control of Diabetes Mellitus.
Pens to be used with LANTUS cartridge
The LANTUS cartridge should only be used with the following pens:
- JuniorSTAR™, which delivers LANTUS in 0.5 unit dose increments.
- ClikSTAR® which delivers LANTUS in 1 unit dose increments.
This cartridge should not be used with any other reusable pen as the dosing accuracy has only been established with the listed pens.
Occupational Hazards
The patient’s ability to concentrate and react may be impaired as a result of hypoglycemia or hyperglycemia or, for example, as a result of visual impairment. This may constitute a risk in situations where these abilities are of special importance (e.g. driving a car or operating machinery).
Patients should be advised to take precautions to avoid hypoglycemia whilst driving. This is particularly important in those who have reduced or absent awareness of the warning symptoms of hypoglycemia or have frequent episodes of hypoglycemia. It should be considered whether it is advisable to drive or operate machinery in these circumstances.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Type 1 and type 2 diabetes in adults:
The adverse events most commonly associated with LANTUS [insulin glargine injection (rDNA origin)] include the following:
Eyes disorders
Retinopathy was evaluated in the clinical studies by means of retinal adverse events reported and fundus photography. The numbers of retinal adverse events reported for LANTUS and human NPH treatment groups were similar for patients with type 1 and type 2 diabetes.
Effects of LANTUS on diabetic retinopathy were evaluated in a large 5-year NPH-controlled study in patients with type 2 diabetes in which progression of retinopathy was investigated by fundus photography using a grading protocol derived from the Early Treatment Diabetic Retinopathy Study (ETDRS). The primary outcome in this study was progression by 3 or more steps on the ETDRS scale at study endpoint. The results of this analysis are shown in the table below for the per-protocol (primary analysis) population and indicate non-inferiority of LANTUS to NPH in the progression of diabetic retinopathy as assessed by this outcome. The per-protocol population, which comprised 72.0% of randomized patients, were patients treated with study drug for at least 4 years and had fundus photographs at baseline and after at least 4.5 years post-baseline. The results in the Intent to Treat (ITT) population are similar to the results in the per-protocol population.
| Table 1 - Number (%) of subjects with 3-step or greater progression in ETDRS at endpoint – per-protocol population | ||||||
| LANTUS | NPH | |||||
| (N=374) | (N=363) | |||||
| Subjects with 3-step or greater progression (progression rate) | 53/374 (14.2%) | 57/363 (15.7%) | ||||
| Difference in progression rate (SE) versus NPH | -1.98% (2.57%) | |||||
| 95% CI versus NPH | (-7.02% to 3.06%) | |||||
| Note: % Calculated using number of PP subjects with non-missing data as denominator. ETDRS = early treatment diabetic retinopathy scale. Adjusted for baseline A1C stratum. Margin of non-inferiority = 10%. | ||||||
Figure 1 - Plot of 3-step or greater progression rate over time - PP population
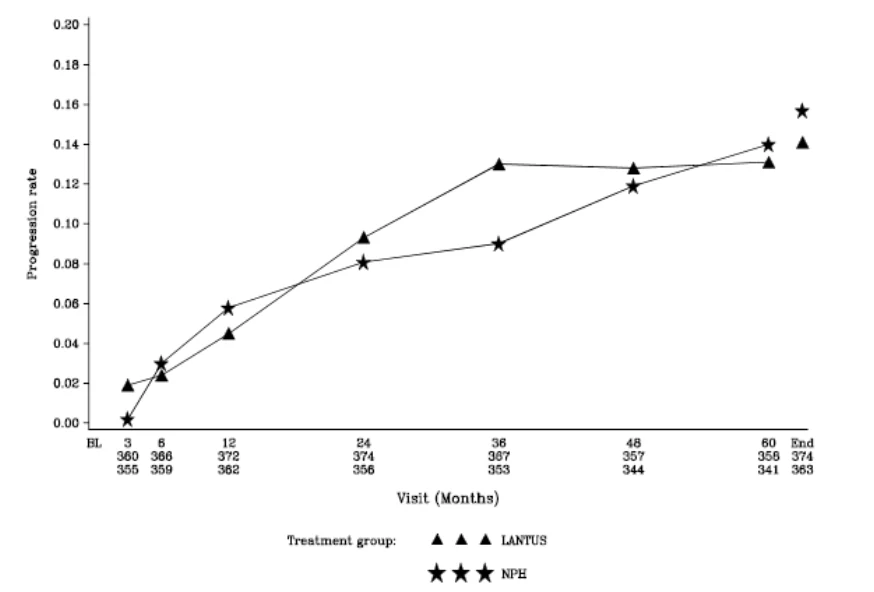
Two pre-specified secondary outcomes were the development of “clinically significant macular edema” (CSME) and “proliferative diabetic retinopathy” (PDR), both based on fundus photograph assessment. CSME developed in 15.6% of the LANTUS group and 14.6% of the NPH group and PDR developed in 5.4% of the LANTUS group and 3.9% of the NPH group.
Cataracts were reported more commonly in the LANTUS group, in particular cortical (but not nuclear) cataracts. There was a baseline imbalance in cataracts with a greater incidence in the LANTUS treatment group. Diabetic retinopathy adverse events were reported in 4.9% of LANTUS treated patients vs. 3.8% of NPH treated patients.
Benign prostatic hyperplasia (BPH) was reported as an Adverse Event by 2.7% of the LANTUS group compared to 0.6% of the NPH group; urinary retention was reported by 1.2% vs. none, respectively. Neoplasms benign or malignant were seen in 11.1% of LANTUS patients, vs. 12.3% of NPH patients.
Immune system disorders
- allergic reaction (see WARNINGS AND PRECAUTIONS).
- injection site reaction
Investigations
- antibodies formation (see WARNINGS AND PRECAUTIONS).
Metabolism and nutrition disorders
Hypoglycemia: Hypoglycemia, a frequent adverse reaction to insulin therapy, may occur if the insulin dose is too high in relation to the insulin requirement.
As with all insulins, prolonged or severe hypoglycemic attacks, especially if recurrent, may lead to neurological damage, loss of consciousness, coma or death (see WARNINGS and PRECAUTIONS).
In the multinational ORIGIN trial conducted in 12,537 participants, the rates of severe hypoglycemia (affected participants per 100 participant years of exposure) were 1.05 for insulin glargine and 0.30 for Standard Care group and the rates of confirmed non severe hypoglycemia were 7.71 for insulin glargine and 2.44 for Standard Care group. Over the course of this study (median follow-up: 6.2 years), 42% of the patients in the insulin glargine group did not experience any hypoglycemia.
Skin and subcutaneous tissue disorders
- Lipodystrophy, pruritus, and rash (see WARNINGS AND PRECAUTIONS).
Type 1 diabetes in children and adolescents:
Adverse events that occurred in a pediatric controlled trial in at least 1% of patients treated with LANTUS are shown below.
Table 2. Adverse Events by Body System ≥1% reported in Study 3003. (Percent Incidence)
| Adverse event (diagnosis) | Number (%) of subjects | ||||||
|---|---|---|---|---|---|---|---|
| Body System/Coded Term | LANTUS n= 174 | Human NPH n=175 | |||||
| Body as a whole | |||||||
| Infection | 24 (13.8) | 31 (17.7) | |||||
| Accidental injury | 5 (2.9) | 4 (2.3) | |||||
| Abdominal pain | 2 (1.1) | 2 (1.1) | |||||
| Allergic reaction | 2 (1.1) |
| |||||
| Flu syndrome |
| 3 (1.7) | |||||
| Pain in extremity | 2 (1.1) |
| |||||
| Digestive system | |||||||
| Gastroenteritis | 8 (4.6) | 10 (5.7) | |||||
| Diarrhea | 2 (1.1) | 2 (1.1) | |||||
| Sore throat | 2 (1.1) |
| |||||
| Endocrine system | |||||||
| Diabetes mellitus | 1 (0.6) | 4 (2.3) | |||||
| Injection site reactions | |||||||
| Injection site mass | 8 (4.6) | 6 (3.4) | |||||
| Injection site reaction | 5 (2.9) | 6 (3.4) | |||||
| Injection site hemorrhage | 2 (1.1) | 2 (1.1) | |||||
| Metabolic and nutritional disorders | |||||||
| Hypoglycemic reaction* | 3 (1.7) | 7 (4.0) | |||||
| Hyperglycemia | 1 (0.6) | 3 (1.7) | |||||
| Ketosis | 1 (0.6) | 5 (2.9) | |||||
| Lipodystrophy | 3 (1.7) | 2 (1.1) | |||||
| Musculo-skeletal system | |||||||
| Bone fracture (not spontaneous) | 3 (1.7) | 3 (1.7) | |||||
| Bone disorder | 2 (1.1) |
| |||||
| Nervous system | |||||||
| Headache | 6 (3.4) | 5 (2.9) | |||||
| Respiratory system | |||||||
| Upper respiratory infection | 24 (13.8) | 28 (16.0) | |||||
| Pharyngitis | 13 (7.5) | 15 (8.6) | |||||
| Rhinitis | 9 (5.2) | 9 (5.1) | |||||
| Bronchitis | 6 (3.4) | 7 (4.0) | |||||
| Sinusitis | 5 (2.9) | 5 (2.9) | |||||
| Asthma | 1 (0.6) | 2 (1.1) | |||||
| Cough increased | 3 (1.7) |
| |||||
| Skin and appendages | |||||||
| Fungal dermatitis | 1 (0.6) | 2 (1.1) | |||||
| Skin benign neoplasm | 1(0.6) | 2 (1.1) | |||||
| Eczema | 2 (1.1) | 1 (0.6) | |||||
| Herpes zoster | 2 (1.1) | 1 (0.6) | |||||
| Urticaria | 2 (1.1) |
| |||||
*Non-serious hypoglycemia episodes are reported separately.
Study 3003: The most commonly reported event was lipodystrophy, a known consequence of insulin injections. The intensity was mostly mild. Injection site events were assessed as possibly related in 9 (5.2%) LANTUS subjects and 5 (2.9%) human NPH subjects however none of these subjects discontinued due to these events.
Study 3013: extension of Study 3003, uncontrolled long-term follow-up study of 143 patients who were well-controlled on LANTUS from 3003, for 201-1159 days. The most common adverse events were upper respiratory infections, infection, and rhinitis. Note that when comparing safety findings between studies, the difference in length of exposure needs to be kept in mind.
Study 4005: controlled, randomized, double-cross-over: 26 subjects (age range 12 - 20), regimen of LANTUS + lispro vs. human NPH + human regular. Adverse events were equally distributed between the two treatment regimens. The most common adverse events were upper respiratory tract infection and gastroenteritis.
Patients in the pediatric clinical trials of LANTUS were treated with a human NPH-based regimen pre-study, and patients assigned to receive human NPH during the study began study treatment on the same human NPH regimen they had taken pre-study. This may have been a factor in the increased incidence of hypoglycemia seen in LANTUS -treated patients during (but not following) initial titration in these trials, as an increase in hypoglycemia may be expected when switching from one insulin to another and titrating the dose of the new insulin.
Cardiovascular Safety
Study 4032 (ORIGIN Trial): randomized, 2x2 factorial design study: 12,537 participants. Participants were randomized to receive LANTUS (n=6264), titrated to a Fasting Plasma Glucose (FPG) of 5.3 mmol/L or less, or Standard Care (n=6273). Overall, the incidence of major adverse cardiovascular outcomes was similar between groups. All-cause mortality was also similar between groups (see Table 3).
The objective of the trial was to demonstrate that LANTUS use could significantly lower the risk of major cardiovascular outcomes compared to standard care. Two co-primary composite cardiovascular endpoints were used in ORIGIN. The first co-primary endpoint was the time to first occurrence of a major adverse cardiovascular event defined as the composite of CV death, nonfatal myocardial infarction and nonfatal stroke. The second co-primary endpoint was the time to the first occurrence of CV death or nonfatal myocardial infarction or nonfatal stroke or revascularization procedure or hospitalization for heart failure.
Anthropometric and disease characteristics were balanced at baseline. The mean age was 64 years and 8% of participants were 75 years of age or older. The majority of participants were male (65%). Fifty nine percent were Caucasian, 25% were Latin, 10% were Asian and 3% were Black. The median baseline BMI was 29 kg/m2 and 88% had type 2 diabetes. For patients with type 2 diabetes, 59% were treated with a single oral antidiabetic drug, 23% had known diabetes but were on no antidiabetic drug and 6% were newly diagnosed during the screening procedure. The mean A1c (SD) at baseline was 6.5% (1.0). Fifty nine percent of participants had had a prior cardiovascular event and 39% had documented coronary artery disease or other cardiovascular risk factors.
Vital status was available for 99.9% and 99.8% of participants randomized to LANTUS and standard care respectively at end of trial. The median duration of follow-up was 6.2 years [range: 8 days to 7.9 years]. The mean A1c (SD) at the end of the trial was 6.5% (1.1) and 6.8% (1.2) in the LANTUS and standard care group respectively. The median dose of LANTUS at end of trial was 0.45 U/kg. Eighty-one percent of patients randomized to LANTUS were using LANTUS at end of the study.
Table 3: ORIGIN: Time to Onset of each Primary and Secondary Endpoint
LANTUS N=6264 | Standard care N=6273 | LANTUS vs Standard care | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Participants with Events N (%) n | No./100 patient-yr | Participants with Events N (%) n | No./100 patient-yr | Hazard Ratio (95% CI) | ||||||||
| Primary endpoints | ||||||||||||
| CV death, nonfatal myocardial infarction (MI), or nonfatal stroke | 1041 (16.6) | (2.94) | 1013 (16.1) | (2.85) | 1.02 (0.94, 1.11) | |||||||
| CV death, nonfatal myocardial infarction (MI), or nonfatal stroke, or hospitalization for heart failure or revascularization procedure | 1792 (28.6) | (5.52) | 1727 (27.5) | (5.28) | 1.04 (0.97, 1.11) | |||||||
| Secondary endpoints | ||||||||||||
| All-cause mortality | 951 (15.2) | (2.57) | 965 (15.4) | (2.60) | 0.98 (0.90, 1.08) | |||||||
| Composite microvascular outcome* | 1323 (21.1) | (3.87) | 1363 (21.7) | (3.99) | 0.97 (0.90, 1.05) | |||||||
| Components of coprimary endpoint | ||||||||||||
| CV death | 580 (9.3) | (1.57) | 576 (9.2) | (1.55) | 1.00 (0.89, 1.13) | |||||||
| MI (fatal or non-fatal) | 336 (5.4) | (0.93) | 326 (5.2) | (0.90) | 1.03 (0.88, 1.19) | |||||||
| Stroke(fatal or non-fatal) | 331 (5.3) | (0.91) | 319 (5.1) | (0.88) | 1.03 (0.89, 1.21) | |||||||
| Revascularizations | 908 (14.5) | (2.69) | 860 (13.7) | (2.52) | 1.06 (0.96, 1.16) | |||||||
| Hospitalization for heart failure | 310 (4.9) | (0.85) | 343 (5.56) | (0.95) | 0.90 (0.77, 1.05) | |||||||
*with components of: laser photocoagulation or vitrectomy or blindness for diabetic retinopathy; progression in albuminuria; or doubling of serum creatinine or development of the need for renal replacement therapy
LANTUS did not alter the relative risk for CV disease and CV mortality when compared to standard care. There were no differences between LANTUS and Standard Care groups for the two co-primary outcomes; for any component endpoint comprising these outcomes; for all mortality; or for the composite microvascular outcome.
Malignancies
In the ORIGIN trial, the overall incidence of cancer (all types combined) or death from cancer was similar between treatment groups. The time to first event of any cancer or new cancer during the study was similar between the two treatment groups with respective hazard ratios of 0.99 (95% CI: 0.88, 1.11) and 0.96 (95% CI: 0.85, 1.09).
Body Weight
At the last on-treatment visit (median follow-up: 6.2 years), there was a mean increase in body weight from baseline of 1.4 kg in the LANTUS group and a mean decrease of 0.8 kg in the Standard Care group.
Post-Market Adverse Drug Reactions
Other:
Medication errors have been reported in which other insulins, particularly short-acting insulins, have been accidentally administered instead of LANTUS.
DRUG INTERACTIONS
A number of substances affect glucose metabolism and may require insulin dose adjustment and particularly close monitoring.
Drug-Drug Interactions
Substances that may increase the blood-glucose-lowering effect and susceptibility to hypoglycemia, for example: oral antidiabetic products, ACE inhibitors, disopyramide, fibrates, fluoxetine, MAO inhibitors, pentoxifylline, propoxyphene, salicylates, somatostatin analog (e.g. octreotide), sulfonamide antibiotics.
Substances that may reduce the blood-glucose-lowering effect, for example: corticosteroids, danazol, diazoxide, diuretics, sympathomimetic agents (e.g., epinephrine, salbutamol, terbutaline), glucagon, isoniazid, phenothiazine derivatives, somatropin, thyroid hormones, estrogens, progestogens (e.g., in oral contraceptives), protease inhibitors and atypical antipsychotic medications (e.g., olanzapine and clozapine).
Beta-blockers, clonidine, lithium salts, and alcohol may either potentiate or weaken the blood-glucose-lowering effect of insulin. Pentamidine may cause hypoglycemia, which may sometimes be followed by hyperglycemia. In addition, under the influence of sympatholytic medicinal products such as beta-blockers, clonidine, guanethidine, and reserpine, the signs of hypoglycemia may be reduced or absent.
Other:
To avoid the risk of developing new or worsening heart failure, the use of TZDs in combination therapy with insulin is not indicated (see WARNINGS AND PRECAUTIONS).
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
LANTUS [insulin glargine injection (rDNA origin)] is a novel recombinant human insulin analogue. Its potency is approximately the same as human insulin. It exhibits a glucose-lowering profile with no pronounced peak with a prolonged duration of action that permits once-daily basal dosing. LANTUS is administered subcutaneously once a day. It may be administered at any time during the day as long as it is administered at the same time every day.
The desired blood glucose levels as well as the doses and timing of antidiabetic medications must be determined and adjusted individually.
Dose adjustment may be required, for example, if the patient's timing of administration, weight or lifestyle changes or other circumstances arise that increase susceptibility to hypoglycemia or hyperglycemia (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypoglycemia and Hyperglycemia). The dose may also have to be adjusted during intercurrent illness (see WARNINGS AND PRECAUTIONS, Intercurrent Conditions). Any change in insulin dose should be made under medical supervision.
The prolonged duration of activity of LANTUS is dependent on injection into subcutaneous space. LANTUS is not intended for intravenous or intramuscular administration. Intravenous administration of the usual subcutaneous dose could result in severe hypoglycemia (see WARNINGS AND PRECAUTIONS).
In cases of insufficient glucose control or a tendency to hyper- or hypoglycemic episodes, patient’s compliance with the prescribed insulin regimen, injections sites and proper injection techniques, the handling of injection devices and all other relevant factors must be reviewed before dose adjustment is considered.
Blood glucose monitoring is recommended for all patients with diabetes.
LANTUS must not be used for the treatment of diabetic ketoacidosis. Intravenous short-acting insulin should be the preferred treatment.
Recommended Dose and Dosage Adjustment
Initiation of LANTUS therapy
In clinical studies with insulin naïve patients with type 2 diabetes, LANTUS was started at a dose of 10 U once daily, and subsequently adjusted according to the patient’s need (see CLINICAL TRIALS).
Changeover to LANTUS
When changing from a treatment regimen with an intermediate or long-acting insulin to a regimen with LANTUS, the amount and timing of short-acting insulin or fast-acting insulin analogue or the dose of any oral antidiabetic drug may need to be adjusted secondary to the risk of hypoglycemia. In clinical studies when patients were transferred from once-daily NPH human insulin or ultralente human insulin to once-daily LANTUS, the initial dose was usually not changed.
However, in studies when patients were transferred from twice-daily NPH human insulin to LANTUS once daily, the initial dose (U) was usually reduced by approximately 20% (compared to total daily IU of NPH human insulin) and then adjusted based on patient response.
To reduce the risk of hypoglycaemia, when patients are transferred from once daily insulin glargine 300 Units/mL to once daily LANTUS, the recommended initial LANTUS dose is 80% of the insulin glargine 300 Units/mL dose that is being discontinued.
A program of close metabolic monitoring under medical supervision is recommended during transfer and in the initial weeks thereafter. The amount and timing of short-acting insulin or fast-acting insulin analogue may need to be adjusted. This is particularly true for patients with acquired antibodies to human insulin needing high-insulin doses and occurs with all insulin analogues. Such patients may experience a greater insulin response to LANTUS.
With improved metabolic control and resulting increase in insulin sensitivity, adjustment of the dose(s) of antidiabetic treatments may become necessary.
Administration
LANTUS is administered by subcutaneous injection. The injection area must not be rubbed.
As with all insulins, injection sites within an injection area (abdomen, thigh, buttock or deltoid) must be alternated from one injection to the next. Patients should be rigorous with site rotation secondary to prolonged deposition. In clinical studies, there was no relevant difference in insulin glargine absorption after abdominal, thigh, or deltoid subcutaneous administration. As for all insulins, the rate of absorption, and consequently the onset and duration of action, may be affected by exercise and other variables.
Preparation and handling:
LANTUS is a clear solution, not a suspension.
Parenteral drug products should be inspected visually prior to administration whenever the solution and the container permit. LANTUS must only be used if the solution is clear and colorless with no particles visible. To minimize local irritation at the injection site, it is recommended to allow the insulin to reach room temperature before injection.
Cartridge version only: If the injection pen malfunctions, LANTUS may be drawn from the cartridge into an insulin syringe and injected. A new sterile syringe must be used.
Patient must be instructed to not re-use needles. INJECTION PENS, CARTRIDGES, NEEDLES, AND SYRINGES MUST NOT BE SHARED. To prevent the possible transmission of disease, never share an injection pen or cartridge between patients, even if the needle on the injection pen is changed.
Mixing and diluting:
LANTUS must not be mixed with any other insulin. Mixing can change the time/action profile of LANTUS and cause precipitation.
When LANTUS and regular human insulin were mixed immediately before injection in dogs, a delayed onset of action and time to maximum effect for regular human insulin was observed. The total bioavailability of the mixture was also slightly decreased compared to separate injections of LANTUS and regular human insulin. The relevance of these observations in dogs to humans is not known.
LANTUS must not be diluted. Diluting can change the time/action profile of LANTUS.
OVERDOSAGE
Symptoms: An excess of insulin relative to food intake, energy expenditure or both may lead to severe and sometimes prolonged and life-threatening hypoglycemia (see WARNINGS AND PRECAUTIONS).
Symptoms of hypoglycemia may occur suddenly. They may include cold sweat, cool pale skin, fatigue, drowsiness, excessive hunger, vision changes, headache, nausea and palpitation. Nocturnal hypoglycemia is common in people taking insulin and symptoms can include restlessness, making unusual noises, attempting to get out of bed or accidentally rolling out of bed, sleepwalking, nightmares and sweating. Patients may wake with a headache in the morning if their blood sugar was low during the night.
Severe hypoglycemia may lead to unconsciousness and/or convulsions and may be fatal. In some cases, the first sign of hypoglycemia may be confusion or loss of consciousness (hypoglycemia unawareness). Severe hypoglycemia, resulting in seizures, is more likely to occur at nighttime (nocturnal hypoglycemia) than during the day.
Management: Mild episodes of hypoglycemia can usually be treated with oral carbohydrates. Adjustments in drug dosage, meal patterns, or exercise may be needed. It is therefore recommended that patients with diabetes carry sugar-containing products.
Severe hypoglycemic episodes, where the patient has become unconscious, can be treated by glucagon (for adult: 1 mg; for children weighing less than 20 kg: 0.5 mg) given intramuscularly or subcutaneously by a trained person, or by glucose given intravenously by a medical professional. Upon regaining consciousness, administration of oral carbohydrates is recommended for the patient in order to prevent a relapse.
After apparent clinical recovery from hypoglycemia, continued observation and additional carbohydrate intake may be necessary to avoid reoccurrence of hypoglycemia.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Pharmacodynamics
Insulin glargine is a human insulin analogue designed to have low solubility at neutral pH. At pH 4, as in the LANTUS injection solution, it is completely soluble. After injection into the subcutaneous tissue, the acidic solution is neutralized, leading to formation of microprecipitates from which small amounts of insulin glargine are slowly released, resulting in a relatively constant concentration/time profile over 24 hours with no pronounced peak. This allows once-daily dosing to meet a patient’s basal insulin needs.
The primary activity of insulin, including insulin glargine, is regulation of glucose metabolism. Insulin and its analogues lower blood glucose levels by stimulating peripheral glucose uptake, especially by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulin inhibits lipolysis in the adipocyte, inhibits proteolysis, and enhances protein synthesis.
Insulin glargine and human insulin have been shown to be equipotent in glucose-lowering effect on a molar basis (when administered intravenously at the same doses). In euglycemic clamp studies in healthy subjects or in patients with type 1 diabetes, the onset of action of subcutaneous insulin glargine was slower than NPH human insulin. The effect profile of insulin glargine was relatively constant with no pronounced peak, and the duration of its effect was prolonged compared to NPH human insulin.
Figure 2 shows results from a study in patients with type 1 diabetes conducted for a maximum of 24 hours after the injection. The median time between injection and the end of pharmacological effect was 14.5 hours (range: 9.5 to 19.3 hours) for NPH human insulin, and 24 hours (range: 10.8 to >24.0 hours) (24 hours was the end of the observation period) for insulin glargine.
Figure 2 – Activity Profile in Patients with Type 1 Diabetes
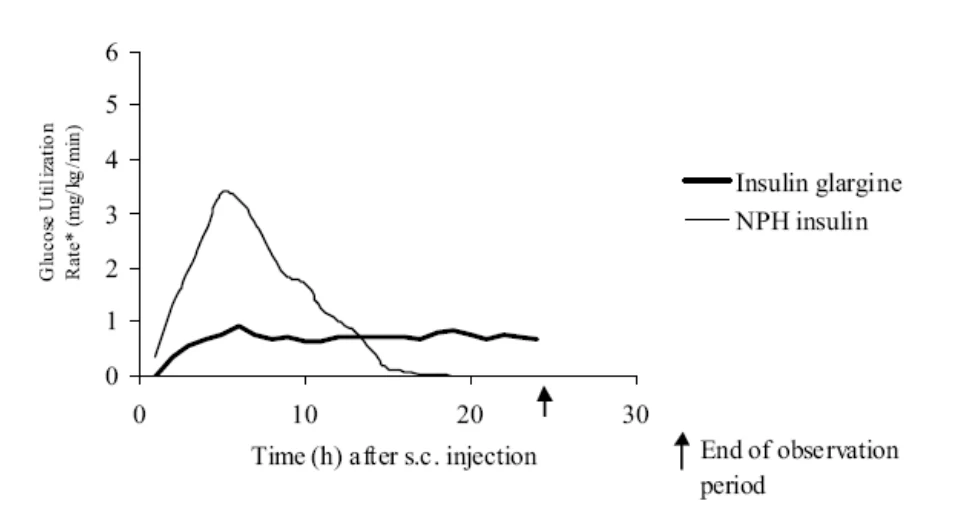
*Determined as amount of glucose infused to maintain constant plasma glucose levels (hourly mean values). Indicative of insulin activity. Between-patient variability (CV, coefficient of variation), insulin glargine, 84% and human NPH, 78%
Pharmacokinetics
Absorption and Bioavailability.
After subcutaneous injection of insulin glargine in healthy subjects, and patients with diabetes, the insulin serum concentrations indicated a slower, more prolonged absorption and a relatively constant concentration/time profile over 24 hours with no pronounced peak in comparison to NPH human insulin. Serum insulin concentrations were thus consistent with the time profile of the pharmacodynamic activity of insulin glargine.
After subcutaneous injection of 0.3 U/kg insulin glargine in patients with type 1 diabetes, a relatively constant concentration-time profile has been demonstrated. The duration of action after abdominal, thigh, or deltoid subcutaneous administration was similar.
Metabolism
After subcutaneous injection of LANTUS in healthy subjects and diabetic patients, insulin glargine is rapidly metabolized at the carboxyl terminus of the Beta chain with formation of two active metabolites M1 (21A-Gly-insulin) and M2 (21A-Gly-des-30B-Thr-insulin). In plasma, the principal circulating compound is the metabolite M1. The exposure to M1 increases with the administered dose of LANTUS. The pharmacokinetic and pharmacodynamic findings indicate that the effect of the subcutaneous injection with LANTUS is principally based on exposure to M1. Insulin glargine and the metabolite M2 were not detectable in the vast majority of subjects and, when they were detectable their concentration was independent of the administered dose of LANTUS.
Special Populations and Conditions
Age, race, and gender: Information on the effect of age, race, and gender on the pharmacokinetics of LANTUS is unavailable. However, in controlled clinical trials in adults (n=3890, Studies 3001, 3002, 3004, 3005, and 3006), and a controlled clinical trial in pediatric patients (n=349, Study 3003) subgroup analyses based on age, race (white, black, Asian /oriental, multiracial and Hispanic) and gender did not show differences in safety and efficacy between insulin glargine and NPH human insulin.
Hepatic Insufficiency: No studies were performed in patients with hepatic insufficiency. However, some studies with human insulin have shown increased circulating levels of insulin in patients with liver failure. Careful glucose monitoring and dose adjustments of insulin or insulin analogues including LANTUS may be necessary in patients with hepatic dysfunction (see WARNINGS AND PRECAUTIONS, Renal/ Hepatic/ Biliary/ Pancreatic impairment).
Renal Insufficiency: No studies were performed in patients with renal insufficiency. However, some studies with human insulin have shown increased circulating levels of insulin in patients with renal failure. Careful glucose monitoring and dose adjustments of insulin or insulin analogues including LANTUS may be necessary in patients with renal dysfunction (see WARNINGS AND PRECAUTIONS, Renal/ Hepatic/ Biliary/ Pancreatic impairment).
Pregnancy: The effect of pregnancy on the pharmacokinetics and pharmacodynamics of LANTUS has not been studied (see WARNINGS AND PRECAUTIONS, Special Populations).
Obesity: In controlled clinical trials, which included patients with Body Mass Index (BMI) up to and including 49.6 kg/m2, subgroup analyses based on BMI did not show any differences in safety and efficacy between insulin glargine and NPH human insulin.
Smoking: Information on the effect of smoking on the pharmacokinetics of LANTUS is unavailable.
Duration of Effect
The longer duration of action (up to 24 hours) of LANTUS is directly related to its slower rate of absorption and supports once-daily subcutaneous administration. The time course of action of insulins including LANTUS may vary between individuals and/or within the same individual. The doses and timing of antidiabetic medications must be determined and adjusted individually, to achieve the desired blood glucose levels.
STORAGE AND STABILITY
Vials
Unopened Vial:
Unopened LANTUS vials should be stored in a refrigerator, between 2°C – 8°C. Keep LANTUS away from direct heat and light. LANTUS should not be stored in the freezer and should not be allowed to freeze. If LANTUS freezes or overheats, discard it.
Opened (In Use) Vial:
The opened vial can be kept refrigerated or unrefrigerated (15 – 30°C) for up to 28 days away from direct heat and light, as long as the temperature is not greater than 30°C. Opened LANTUS vials, whether or not refrigerated, must be discarded after 28 days even if they contain insulin.
Opened LANTUS vials should not be stored in the freezer and should not be allowed to freeze. If a vial freezes or overheats, discard it.
Cartridges
Unopened Cartridge:
Unopened LANTUS cartridges should be stored in a refrigerator, between 2°C - 8°C. Keep LANTUS away from direct heat and light. LANTUS should not be stored in the freezer and should not be allowed to freeze. If LANTUS freezes or overheats, discard it.
Opened (In Use) Cartridge:
The opened cartridge in use must be kept unrefrigerated (15 - 30°C) for up to 28 days away from direct heat and light, as long as the temperature is not greater than 30°C. If the cartridge overheats or if there is any remaining insulin after 28 days, discard it. The opened cartridge in use must never be removed from and reinserted into the injection pen.
OptiSet®
Unopened OptiSet:
Unopened LANTUS OptiSet should be stored in a refrigerator, between 2°C - 8°C. Keep LANTUS away from direct heat and light. LANTUS OptiSet should not be stored in the freezer and should not be allowed to freeze. If LANTUS OptiSet freezes or overheats, discard it.
Opened (In Use) OptiSet:
Opened LANTUS OptiSet in use must be kept unrefrigerated (15-30°C) for up to 28 days away from direct heat and light, as long as the temperature is not greater than 30°C. If the LANTUS OptiSet overheats or if there is any remaining insulin after 28 days, discard it.
Opened LANTUS OptiSet should not be stored in the freezer and should not be allowed to freeze. If LANTUS OptiSet freezes discard it.
SoloSTAR®
Unopened SoloSTAR:
Unopened LANTUS SoloSTAR should be stored in a refrigerator, between 2°C - 8°C. Keep LANTUS away from direct heat and light. LANTUS SoloSTAR should not be stored in the freezer and should not be allowed to freeze. If LANTUS SoloSTAR freezes or overheats, discard it.
Opened (In Use) SoloSTAR:
Opened LANTUS SoloSTAR in use must be kept unrefrigerated (15-30°C) for up to 28 days away from direct heat and light, as long as the temperature is not greater than 30°C. If the LANTUS SoloSTAR overheats or if there is any remaining insulin after 28 days, discard it.
Opened LANTUS SoloSTAR should not be stored in the freezer and should not be allowed to freeze. If LANTUS SoloSTAR freezes, discard it.
As with all medications and devices, keep out of reach of children.
SPECIAL HANDLING INSTRUCTIONS
Information to be provided to the Patient
LANTUS must only be used if the solution is clear and colorless with no particles visible (see DOSAGE and ADMINISTRATION: Administration). LANTUS is a clear solution, not a suspension. LANTUS can be confused with other insulin types, since it visually resembles short-acting insulins and its name resembles the ‘Lente’ brand of insulins. It is not necessary to shake or rotate the vial/cartridge/OptiSet/SoloSTAR before use. Patients must be advised that LANTUS must not be mixed with any other insulin or diluted with any other solution (see WARNINGS AND PRECAUTIONS).
Patients should be instructed on self-management procedures including glucose monitoring, proper injection technique, and hypoglycemia and hyperglycemia management. Patients must be instructed on handling of special situations such as intercurrent conditions (illness, stress, or emotional disturbances), an inadequate or skipped insulin dose, inadvertent administration of an increased insulin dose, inadequate food intake or skipped meals. The extent of patient participation in his/her diabetes management is variable and is generally determined by the physician.
Insulin treatment requires constant alertness to the possibility of hyper- and hypoglycemia. Patients and their relatives must know what steps to take if hyperglycemia or hypoglycemia occurs or is suspected, and they must know when to inform a physician.
Patients with diabetes should be advised to inform their doctor if they are pregnant or are contemplating pregnancy.
See also INFORMATION FOR THE PATIENT and refer patients to the LANTUS Information for the Patient circular for LANTUS VIALS, LANTUS CARTRIDGE, LANTUS OPTISET and LANTUS SOLOSTAR for additional information. Refer patients to the “Instructions for Use” for ClikSTAR and JuniorSTAR or the User Manual for LANTUS OptiSet and LANTUS SoloSTAR for additional information on use of the pens.
DOSAGE FORMS, COMPOSITION AND PACKAGING
The vials, cartridges, OptiSet, and SoloSTAR contain a sterile solution of insulin glargine for use as an injection. LANTUS [insulin glargine injection (rDNA origin)] consists of insulin glargine dissolved in a clear aqueous fluid.
Each milliliter of LANTUS (insulin glargine injection) contains insulin glargine 100 units. Each milliliter also contains excipients: glycerol 85%, polysorbate 20 (10 mL vial only), m-cresol, zinc, and water for injection. LANTUS has a pH of approximately 4. The pH is adjusted by addition of aqueous solutions of hydrochloric acid and sodium hydroxide.
LANTUS [insulin glargine (rDNA origin)] 100 units per mL (U 100) is available in the following package sizes:
- 10-mL vials
- 3-mL cartridges in package of 5, for use only with ClikSTAR and JuniorSTAR pens.
- 3-mL OptiSet (pre-filled disposable pen), package of 5
- 3-mL SoloSTAR (pre-filled disposable pen), package of 5
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: insulin glargine (rDNA origin)
Chemical name: 21A-Gly-30Ba-L-Arg-30Bb-L-Arg-human insulin
Molecular formula: C267H404N72O78S6
Molecular weight: 6063 Daltons
Structural formula:
Physical Form: fine white powder
Solubility: 3 to 7 μg/mL at pH 7
at least 10 mg/mL at pH 5, greater than 100 mg/mL at pH 2
CLINICAL TRIALS
The safety and efficacy of once-daily insulin glargine at bedtime was compared to that of once-daily and twice-daily NPH human insulin in open-label, randomized, active-control, parallel studies of 2327 adult patients and 518 pediatric patients with type 1 diabetes mellitus and 1563 adult patients with type 2 diabetes mellitus.
In general, insulin glargine maintained the level of glycemic control as measured by glycohemoglobin and fasting glucose.
Type 1 diabetes in adults (see Table 5). In two large, randomized, controlled Phase III studies (Studies 3001 and 3004), patients with type 1 diabetes (n=1119) were randomized to basal-bolus treatment with LANTUS (insulin glargine) once daily or with NPH human insulin once or twice daily and treated for 28 weeks. Regular human insulin was administered before each meal. LANTUS was administered at bedtime. NPH human insulin was administered once daily at bedtime or in the morning and at bedtime when used twice daily. In these studies, LANTUS and human NPH had a similar effect on glycohemoglobin with a similar overall rate of hypoglycemia.
In another large, randomized, controlled Phase III study, patients with type 1 diabetes (Study 3005, n=619) were treated for 16 weeks with a basal-bolus insulin regimen where insulin lispro was used before each meal. LANTUS was administered once daily at bedtime and NPH human insulin was administered once or twice daily. In this study, LANTUS and NPH human insulin had a similar effect on glycohemoglobin with a similar overall rate of hypoglycemia.
Type 2 diabetes in adults (see Table 5). In one large, randomized, controlled Phase III study (Study 3002, n=570), LANTUS was evaluated for 52 weeks as part of a regimen of combination therapy with insulin and oral antidiabetic agents (93.9% sulfonylureas, 51.1% biguanides, 12.3% acarbose, or 2.8% other, percentages add up to greater than 100% due to combination therapy). LANTUS administered once daily at bedtime was as effective as NPH human insulin administered once daily at bedtime in reducing glycohemoglobin and fasting glucose. There was a low rate of hypoglycemia that was similar in LANTUS and NPH human insulin treated patients.
In another large, randomized, controlled Phase III study in patients with type 2 diabetes not using oral antidiabetic agents (Study 3006, n=518), a basal-bolus regimen of LANTUS once daily at bedtime or NPH human insulin administered once or twice daily was evaluated for 28 weeks. Regular human insulin was used before meals as needed.
LANTUS had similar effectiveness as either once- or twice-daily NPH human insulin in reducing glycohemoglobin and fasting glucose with a similar incidence of hypoglycemia.
Type 2 Diabetes - Adults (see Table 4). In a randomized, open-label, parallel, 24-week clinical study in adult patients with type 2 diabetes (Study 4002, n=756) with an A1C>7.5% (mean 8.6%) on one or two oral antidiabetes agents (88.5% sulfonylureas, 82.8% biguanides, or 9.0% TZDs, percentages add up to greater than 100% due to combination therapy), LANTUS or NPH human insulin, once daily at bedtime, was added to their prior regimen. In order to reach the target fasting plasma glucose ≤5.5 mmol/L, the dose of LANTUS and NPH human insulin was adjusted according to the structured dose-titration regimen as described in Table 4.
Table 4. Dose titration schedule
| Period | Dose or dose adjustment | |
| Start of treatment | 10 U/day | |
| Then adjustment every 7 days based on FPG (Fasting Plasma Glucose) as follows: | ||
| Mean FPG ≥10 mmol/L for the last 2 consecutive days and no episodes of severe hypoglycemia or no PG <4.0 mmol/L | Increase daily dose by 8 U | |
| Mean FPG ≥7.8 mmol/L and <10 mmol/L for the last 2 consecutive days and no episodes of severe hypoglycemia or no PG <4.0 mmol/L | Increase daily dose by 6 U | |
| Mean FPG ≥6.7 mmol/L and <7.8 mmol/L for the last 2 consecutive days and no episodes of severe hypoglycemia or no PG <4.0 mmol/L | Increase daily dose by 4 U | |
| Mean FPG >5.5 mmol/L and <6.7 mmol/L for the last 2 consecutive days and no episodes of severe hypoglycemia or no PG <4.0 mmol/L | Increase daily dose by 2 U | |
| Then maintain target FPG ≤5.5 mmol/L | ||
PG = Plasma Glucose
Using this dose-titration schedule, A1C was reduced to a mean of 6.96% for LANTUS and 6.97% for NPH human insulin. More than half of the subjects in each group achieved an A1C value of ≤7.0% LANTUS, 58.0%; NPH human insulin, 57.3%; mean dose at study endpoint was 47.2 U for LANTUS and 41.8 IU for NPH human insulin). In the LANTUS -treated group, 33.2% of the patients reached the primary efficacy endpoint (A1C value of ≤ 7.0% in the absence of plasma glucose-confirmed nocturnal hypoglycemia ≤ 4.0 mmol/L, compared to 26.7% in the NPH human insulin-treated group (p=0.0486).
In this study, fewer patients with type 2 diabetes treated with LANTUS experienced nocturnal hypoglycemia compared with patients treated with NPH human insulin. Other clinical trials in type 2 diabetes showed similar results with less nocturnal hypoglycemia with patients treated with LANTUS compared to patients treated with NPH human insulin.
Type 1 and type 2 diabetes in adults. Table 5 compares regimens of LANTUS once daily to NPH human insulin either once or twice daily in subgroups of patients from Phase III studies based upon prior basal insulin regimens.
Summary of main therapeutic outcomes of the clinical studies
Table 5. Adult Patients
| Type 1 diabetes mellitus | ||||||||
| Diabetes population | Treatment | n a | n b | Endstudy mean (mean change from baseline) | ||||
| Glycated hemoglobin (%)c | Fasting blood glucose (mmol/L) c | |||||||
| Previous use of once-daily basal injection regimen | ||||||||
| with regular human insulin | LANTUS | 222 | 206 | 7.98 (0.01) | 8.51 (-0.93) | |||
| NPH human insulin | 218 | 205 | 7.95 (-0.05) | 8.16 (-1.21) | ||||
| with insulin lispro | LANTUS | 73 | 71 | 7.11 (-0.25) | 8.01 (-1.26) | |||
| NPH human insulin | 69 | 64 | 7.46 (-0.23) | 8.65 (-1.17) | ||||
| Previous use of more than once-daily basal injection regimen | ||||||||
| with regular human insulin | LANTUS | 334 | 303 | 7.77 (0.06) | 7.83 (-1.31)d | |||
| NPH human insulin (x2) | 345 | 315 | 7.69 (-0.05) | 8.78 (-0.72) | ||||
| with insulin lispro | LANTUS | 237 | 224 | 7.66 (-0.03) | 8.0 (-1.42) d | |||
| NPH human insulin (x2) | 240 | 229 | 7.64 (-0.05) | 8.57 (-0.81) | ||||
| Type 2 diabetes mellitus | ||||||||
| Diabetes population | Treatment | n a | n b | Endstudy mean (mean change from baseline) | ||||
| Glycated hemoglobin (%)c | Fasting blood glucose (mmol/L) c | |||||||
| Insulin in combination with oral antidiabetic agents | ||||||||
| No previous insulin use | LANTUS | 222 | 218 | 8.07 (-1.00) | 7.22 (-3.14) | |||
| NPH human insulin | 204 | 194 | 7.92 (-1.00) | 7.29 (-3.19) | ||||
| Previous insulin use | LANTUS | 67 | 61 | 8.71 (-0.14) | 7.43 (-0.82) | |||
| NPH human insulin | 77 | 68 | 8.75 (-0.05) | 7.72 (-0.79) | ||||
| Insulin without oral antidiabetic agents | ||||||||
| Previous use of once-daily basal insulin | LANTUS | 52 | 47 | 8.07 (-0.34) | 8.49 (-0.95) | |||
| NPH human insulin | 48 | 46 | 7.92 (-0.45) | 7.94 (-1.13) | ||||
| Previous use of more than once-daily basal insulin | LANTUS | 207 | 184 | 8.15 (-0.44) | 7.71 (-1.34) | |||
| NPH human insulin (x2) | 211 | 192 | 7.96 (-0.61) | 8.05 (-1.19) | ||||
a Number of patients randomized and treated. b Number of patients randomized, treated, and completed study (without early endpoint) c Intention to treat population d p<0.05; LANTUS compared with NPH human insulin | ||||||||
Type 1 diabetes in children and adolescents (see Table 6)
Study 3003: pivotal study: randomized, open-label, parallel study of 349 Type 1 diabetic children aged 6 to 15 years: treated for 28 weeks with LANTUS once daily versus the most commonly used insulin in children, human NPH once or twice daily. LANTUS had a significant reduction in FBG and similar A1C and 24-hour BG profile when compared to human NPH once or twice daily. The results of this study show that the overall level of glycemic control as measured by A1C and incidence of hypoglycemia achieved after initial titration following switching to LANTUS from pre-study human NPH is similar to that achieved by once or twice daily NPH human insulin.
Table 6. Pediatric Patients
Type 1 Diabetes Mellitus
Study 3003
| Treatment duration | 28 weeks | ||||||||
| Treatment in combination with | Regular insulin | ||||||||
| LANTUS | Human NPH | ||||||||
| Number of subjects treated | 174 | 175 | |||||||
| GHb | |||||||||
| Endstudy mean | 8.91 | 9.18 | |||||||
| Adjusted mean change from baseline | +0.28 | +0.27 | |||||||
| Basal insulin dose | |||||||||
| Endstudy mean | 18.2 | 21.1 | |||||||
| Mean change from baseline | -1.3 | +2.4 | |||||||
| Total insulin dose | |||||||||
| Endstudy mean | 45.0 | 46.0 | |||||||
| Mean change from baseline | +1.9 | +3.4 | |||||||
| Fasting blood glucose (mmol/L) | |||||||||
| Endstudy mean | 9.48 | 10.15 | |||||||
| Adjusted mean change from baseline | -1.29 | –0.68 | |||||||
Study 3013: pivotal study: extension of Study 3003: open-labelled, uncontrolled long-term follow-up study of 143 patients who were well-controlled on LANTUS from 3003, for 201-1159 days, 26 subjects did not continue for administrative and unknown reasons. The level of glycemic control established in Study 3003 was maintained in this study, despite an increase of 0.35% in A1C from baseline in Study 3003. This increase can be attributed to many factors; the deterioration of control with time; puberty, which often has a detrimental impact on glycemic control and is associated with increased insulin resistance and increased insulin requirements; although less common in a post-pubescent population, lack of aggressive titration could be another factor, since pediatricians and parents are often afraid of the deleterious effects of hypoglycemia on children.
Study 4005: open-label, controlled, randomized, double-cross-over: 26 subjects (age range 12 - 20), Tanner B2G2 (puberty stages) or greater were on 16 weeks of each regimen of LANTUS + lispro vs. human NPH + human regular. This non-pivotal trial lacked the necessary power to demonstrate significance for the primary outcome.
The higher episodes of all symptomatic hypoglycemia with LANTUS (308 vs. 237) were only observed in the second period and were associated with a lower A1C for LANTUS (8.6% vs. 9.9%).
The combination of LANTUS and lispro was chosen to best approximate a normal physiologic insulin response during the day. LANTUS’ peakless 24-hour duration better resembles true basal pancreatic insulin secretion than NPH human insulin, and lispro insulin has a more rapid appearance and disappearance from the plasma than regular human insulin, resulting in lower prandial glucose excursions and a lower incidence of postprandial hypoglycemia, compared to regular human insulin.
Compared to human NPH, LANTUS had similar 24-hour BG profile and A1C in Study 3003. In the uncontrolled extension study, Study 3013, the level of glycemic control established in Study 3003 was maintained, despite an increase of 0.35% in A1C from baseline in Study 3003.
During initiation of treatment (and consequent dose titration) with any insulin, the risk of hypoglycemia is higher than after the dose has stabilized following titration. In pediatric clinical trials comparing LANTUS to NPH human insulin, all patients were on human NPH-based regimens prior to the study, which were not changed for patients entering treatment in the human NPH arm. Patients beginning treatment with LANTUS, however, all required dose titration on the new insulin, which may have been in large measure responsible for the increase in hypoglycemia seen in LANTUS-treated patients during titration. In addition, in some studies (Study 4005) A1C and glucose levels were lower in the LANTUS group than in the human NPH group during the titration phase, which would also tend to foster more episodes of hypoglycemia. Post-initiation in Study 3003, LANTUS treatment was associated with a significantly greater reduction in mean FBG and no significant difference in A1C, 24-hr BG profile, and hypoglycemia incidence compared to NPH human insulin given once or twice daily. Post-initiation in crossover Study 4005, LANTUS treatment was associated with no significant difference in FBG, 24-hr BG profile or hypoglycemia incidence compared to NPH human insulin. During the first treatment phase of Study 4005, A1C decreased in both treatment groups. In the second treatment phase, improvement in A1C was maintained in patients on LANTUS + lispro, while A1C increased in subjects who switched to human NPH + human regular.
LANTUS Flexible Daily Administration
The safety and efficacy of LANTUS administered pre-breakfast, pre-dinner or at bedtime were evaluated in a large, randomized, controlled clinical study (Study 4007). In this study in patients with type 1 diabetes (n=378), who were also treated with insulin lispro at meals, LANTUS administered at different times of the day resulted in equivalent glycemic control to that at bedtime (see Table 7).
The safety and efficacy of LANTUS administered pre-breakfast or at bedtime were also evaluated in a large, randomized, active-controlled clinical study (Study 4001, n=697) in type 2 diabetic patients no longer adequately controlled on oral agent therapy. All patients in this study also received AMARYL® (glimepiride) 3 mg daily. LANTUS given before breakfast was as effective in lowering glycated hemoglobin A1C as LANTUS given at bedtime or NPH human insulin given at bedtime (see Table 7).
Table 7. Flexible LANTUS Daily Administration in Type 1 and Type 2 Diabetes Mellitus
Diabetes population Treatment duration Treatment in combination with: | Type 1 diabetes mellitus 24 weeks Insulin lispro | Type 2 diabetes mellitus 24 weeks AMARYL® (glimepiride) | ||||||||||||||||||
| LANTUS | LANTUS | NPH | ||||||||||||||||||
| Breakfa st | Dinner | Bedtime | Breakfast | Bedtime | Bedtime | |||||||||||||||
| na | 112 | 124 | 128 | 234 | 226 | 227 | ||||||||||||||
| nb | 104 | 123 | 125 | 226 | 211 | 205 | ||||||||||||||
| Glycated Hemoglobin A1c c | ||||||||||||||||||||
| Baseline mean | 7.56 | 7.53 | 7.61 | 9.13 | 9.07 | 9.09 | ||||||||||||||
| Endstudy mean | 7.39 | 7.42 | 7.57 | 7.87 | 8.12 | 8.27 | ||||||||||||||
| Mean change from baseline | -0.17 | -0.11 | -0.04 | -1.26 | -0.95 | -0.83 | ||||||||||||||
| Basal insulin dose (U) c | ||||||||||||||||||||
| Endstudy mean | 27.3 | 24.6 | 22.8 | 40.4 | 38.5 | 36.8 | ||||||||||||||
| Mean change from baseline | 5 | 1.8 | 1.5 | |||||||||||||||||
| Total insulin dose (U) c | NA | NA | NA | |||||||||||||||||
| Endstudy mean | 53.3 | 54.7 | 51.5 | |||||||||||||||||
| Mean change from baseline | 1.6 | 3 | 2.3 | |||||||||||||||||
a Number of patients randomized and treated
b Number of patients randomized, treated, and completed study (without early endpoint)
c Intention to treat population
All data collected during study treatment are included in the calculations whenever possible, unless specified for a particular purpose (such as per-protocol population which may exclude patients with very early withdrawal), regardless if patients withdrew or not during the study.
Comparative Bioavailability Study
In a randomized, controlled, double-blind, four-way crossover trial in healthy male volunteers, LANTUS with Polysorbate 20 (Test) was found to be bioequivalent to LANTUS (Reference).
Table 8. Pharmacokinetic parameters from measured insulin serum concentration data
LANTUS (Formulation: 100 U/mL; dosing: 0.4 U/kg body weight) From measured insulin serum concentration Geometric Mean Arithmetic Mean (CV %) |
|---|
| PK Parameter | Test LANTUS with Polysorbate 20 | Reference LANTUS (sanofi-aventis Deutschland GmbH, Germany) | % Ratio of Geometric Means | Confidence Interval (90%) |
|---|---|---|---|---|
| AUC(0-24) (µU.h/mL ) | 343 359 (34%) | 355 367 (26%) | 96.6 | (91.0 ; 102.6) |
| AUC(0-inf) (µU.h/mL ) | 672 716 (37) | 694 757 (46) | 96.9 | (87.1 ; 107.7) |
| CMAX (µU/mL) | 20 21 (34%) | 22 23 (28%) | 89.6 | (83.5; 96.1) |
| TMAX1 (h) | 14.4 (1.0-30.0) | 12.5 (0.5-30.0) | ||
| T½2 (h) | 14.3 (59%) | 16.0 (96%) |
| 1 | Median (range) only. |
| 2 | Arithmetic mean (CV%) only. |
Table 9. Pharmacodynamic parameters from standardized glucose infusion rate data
LANTUS (Formulation: 100 U/mL; dosing: 0.4 U/kg body weight) From standardized glucose infusion rate measured data (GIR) Arithmetic Mean (CV %) Geometric Mean |
|---|
| PD Parameter | Test LANTUS with Polysorbate 20 | Reference LANTUS (sanofi-aventis Deutschland GmbH, Germany) | % Ratio of Means | % Confidence Interval (90%) | |
|---|---|---|---|---|---|
| AUC(0-24) (mg/kg) | 2373 (41%) 2195 | 2367 (40%) 2197 | 100.1 | (88.1; 113.8) | |
| AUC (0-end) (mg/kg) | 2796 (39%) 2605 | 2743 (37%) 2576 | 101.9 | (90.6; 114.7) | |
| GIRMAX1(mg/(min.kg)) | 3.1 (35%) | 3.2 (42%) | 95.6 | (83.3; 109.7) | |
| Time to GIRMAX2(h) | 12.8 (3.2-29.0) | 12.5 (5.2-30.0) | |||
| 1 | Based on smoothed GIR profiles. Expressed as the arithmetic mean (CV%) only. | ||||
| 2 | Based on smoothed GIR profiles. Expressed as median (range) only. | ||||
DETAILED PHARMACOLOGY
Insulin glargine is metabolized into 2 active metabolites M1 and M2.
Insulin receptor binding: In vitro studies indicate that the affinity of insulin glargine and its metabolites M1 and M2 for the human insulin receptor is lower than the one of human insulin (0.68, 0.48 and 0.74, respectively).
IGF-1 receptor binding: The affinity of insulin glargine for the human IGF-1 receptor is approximately 5 to 8-fold greater than that of human insulin (but approximately 70 to 80-fold lower than the one of IGF-1), whereas M1 and M2 bind the IGF-1 receptor with lower affinity compared to human insulin (0.4-0.5 and 0.7-0.8, respectively).
TOXICOLOGY
Acute toxicity: The acute toxicity of i.v. and s.c. administration of insulin glargine was tested in mice and rats. The LD50 in each species was in the range of greater than or equal to 1000 U/kg.
Chronic toxicity: In repeated subcutaneous dose toxicity studies of insulin glargine in mice, rats, and dogs only expected pharmacodynamic results were observed.
Carcinogenesis: The carcinogenic potential of insulin glargine was evaluated in mice and rats at three different dose levels. These two-year carcinogenicity studies were performed in mice and rats. The results do not suggest a cancer risk to humans.
In mice and rats, standard two-year carcinogenicity studies with insulin glargine were performed at doses up to 0.455 mg/kg, which is for the rat approximately 10 times and for the mouse approximately 5 times the recommended human subcutaneous starting dose of 10 U (0.008 mg/kg/day), based on mg/m2. The findings in female mice were not conclusive due to excessive mortality in all dose groups during the study. No clear explanation was found for the excessive mortalities. A similar effect was seen in the female mice control groups: the saline controls mortality (34%) was comparable to the mortality of high dosed female mice (28%) whereas in the vehicle controls mortality reached 42% which is in the same range as the mortality of low dosed female mice (46%). In contrast, the mortality was the same in the male mice saline and vehicle control groups (both 16%). Therefore, these findings are considered as an accidental one due to biological variability. Histiocytomas were found at injection sites in male rats (statistically significant) and male mice (not statistically significant) in acid vehicle containing groups. These tumors were not found in female animals, in saline control, or insulin comparator groups using a different vehicle. The relevance of these findings to humans is unknown.
Mutagenesis: Insulin glargine was not mutagenic in tests for detection of gene mutations in bacteria and mammalian cells (Ames- and HGPRT-test) and in tests for detection of chromosomal aberrations (cytogenetics in vitro in V79 cells and in vivo in Chinese hamsters).
Reproduction Toxicity and Impairment of Fertility: In an embryotoxicity study in rats, hypoglycemia, but no maternal toxicity, occurred. Insulin glargine was not embryotoxic and not teratogenic. In an embryotoxicity study in rabbits, maternal (hypoglycemic shock, intrauterine deaths) and embryo-fetal hypoglycemia-induced toxicity, including single anomalies in the middle- and high-dose groups, were observed. Similar effects were observed with NPH human insulin.
In a combined fertility and prenatal and postnatal study in male and female rats at subcutaneous doses up to 0.36 mg/kg/day, which is approximately 7 times the recommended human subcutaneous starting dose of 10 U (0.008 mg/kg/day), based on mg/m2, maternal toxicity due to dose-dependent hypoglycemia, including some deaths, was observed. Consequently, a reduction of the rearing rate occurred in the high-dose group only. Similar effects were observed with NPH human insulin.
Studies in rats with doses up to 40 times the average daily basal human dose (0.5 U/kg) and a study in rabbits at two times the human dose (0.5 U/kg) do not indicate direct harmful effects on the pregnancy during the different stages of pregnancy. The effects of insulin glargine did not generally differ from those observed with regular human insulin; however, in rabbits, five foetuses from 2 litters of the high dose group exhibited dilation of the cerebral ventricles.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clinically needed.
REFERENCES
- 1. American Diabetes Association. Diabetic retinopathy. Diabetes Care January 1999:22(1):70-73.
- 2. American Diabetes Association. Gestational diabetes. Diabetes Care January 1999:22(1):74-76.
- 3. American Diabetes Association. Insulin administration. Diabetes Care January 1999:22(1):83-86.
- 4. American Diabetes Association. Insulin administration. Diabetes Care January 2004:27(1):106-109.
- 5. American Diabetes Association. Preconception care of women with diabetes. Diabetes Care January 1999:22(1):62-65.
- 6. American Diabetes Association. Standards of care for patients with diabetes mellitus. Diabetes Care January 1999:22(1):32-41.
- 7. Barnett AH, Owens DR. Insulin analogues. Lancet 1997;349:47-51.
- 8. Birkeland KI. Improving glycaemic control with current therapies. Diabet Med 1998;15(4):13-19.
- 9. Bolli GB, Gale EAM. Hypoglycemia. In: Alberti KGMM, DeFronzo RA, Keen H, Zimmet P. International Textbook of Diabetes Mellitus. Chichester, England: John Wiley & Sons 1992:1131-1149.
- 10. Davidson JK, Galloway JA, Chance RE. Insulin therapy. In: Davidson JK. Clinical Diabetes Mellitus. A Problem-Oriented Approach. New York: Thieme Medical Publishers, Inc.1991:266-332.
- 11. Di Cianni G, Torlone E, Lencioni C et al. Perinatal outcomes associated with the use of glargine during pregnancy. Diabetic Med. 2008;25:993-6.
- 12. ORIGIN Trial Investigators, Gerstein HC, Bosch J, Dagenais GR, Díaz R, Jung H, Maggioni AP, Pogue J, Probstfield J, Ramachandran A, Riddle MC, Rydén LE, Yusuf S. Basal Insulin and Cardiovascular and Other Outcomes in Dysglycemia. N Engl J Med 2012;367:319-28.
- 13. Home PD, Alberti KGMM. Insulin therapy. In: Alberti KGMM, DeFronzo RA, Keen H, Zimmet P. International Textbook of Diabetes Mellitus. Chichester, England: John Wiley & Sons 1992: 831-863.
- 14. Koda-Kimble MA, Rotblatt MD. Diabetes mellitus. In: Young LY, Koda-Kimble MA, editors. Applied Thereapeutics: The Clinical Use of Drugs. Vancouver: Applied Therapeutics Inc. 1992:72.1-72.53.
- 15. Lepercq J, Jacqueminet S, Hieronimus S et al. Use of insulin glargine throughout pregnancy in 102 women with type 1 diabetes. Diabetes Metab. 2010;36:209-12.
- 16. Marshall SM, Walker M, Alberti KGMM. Diabetic ketoacidosis and hyperglycemic non-ketotic coma. In: Alberti KGMM, DeFronzo RA, Keen H, Zimmet P. International Textbook of Diabetes Mellitus. Chichester, England: John Wiley & Sons 1992:1152-1171.
- 17. Mohn A, Strang S, Wernicke-Panten K, Lang AM, Edge JA, Dunger DB. Nocturnal glucose control and free insulin levels in children with type 1 diabetes by use of the long-acting insulin HOE 901 as part of a three-injection regimen. Diabetes Care 2000; 23:557-9.
- 18. Negrato CA, Rafacho A, Negrato G et al. Glargine vs. NPH insulin therapy in pregnancies complicated by diabetes: an observational cohort study. Diabetes Res and Clin Pract. 2010;89:46-51.
- 19. Pantalone KM, Faiman C, Olansky L. Insulin glargine use during pregnancy. Endocr Pract. 2011;17:448-55.
- 20. Persson B, Lunell NO. Diabetes mellitus and pregnancy. In: Alberti KGMM, DeFronzo RA, Keen H, Zimmet P. International Textbook of Diabetes Mellitus. Chichester, England: John Wiley & Sons 1992: 1085-1101.
- 21. Peters AL, Davidson MB. Aging and diabetes. In: Alberti KGMM, DeFronzo RA, Keen H, Zimmet P. International Textbook of Diabetes Mellitus. Chichester, England: John Wiley & Sons 1992:1103-1128.
- 22. Pickup JC, Williams G, EDITOR. The pharmacokinetics of insulin. In: Pickup JC, Williams G. Textbook of Diabetes. Oxford: Blackwell Science Ltd, 1997:32.1-2.14.
- 23. Pickup JC, Williams G, EDITOR. Insulin injection treatment and its complications. In: Pickup JC, Williams G. Textbook of Diabetes. Oxford: Blackwell Science Ltd, 1997:33.1-33.20.
- 24. Pickup JC, Williams G, EDITOR. Acute metabolic complications of diabetes: diabetic ketoacidosis, hyperosmolar non-ketotic syndrome and lactic acidosis. In: Pickup JC, Williams G. Textbook of Diabetes. Oxford: Blackwell Science Ltd, 1997:39.1-39.23.
- 25. Pickup JC, Williams G, EDITOR. Hypoglycaemia in diabetes mellitus. In: Pickup JC, Williams G. Textbook of Diabetes. Oxford: Blackwell Science Ltd, 1997:40.1-40.23.
- 26. Pickup JC, Williams G, EDITOR. Pregnancy and diabetes mellitus. In: Pickup JC, Williams G. Textbook of Diabetes. Oxford: Blackwell Science Ltd, 1997:72.1-72.34.
- 27. Pollex EK, Feig DS, Lubetsky A et al. Insulin glargine safety in pregnancy: a transplacental transfer study. Diabetes Care. 2010;33:29-33.
- 28. E. Pollex, M. E. Moretti, G. Koren et al. Safety of insulin glargine use in pregnancy: a systematic review and meta-analysis. Ann Pharmacother. 2011 ;45:9-16.
- 29. Ratner RE. Type 2 diabetes mellitus: The grand overview. Diabetic Med 1998;15(4):4-7.
- 30. Rossetti L, Giaccari A, DeFronzo RA.Glucose toxicity. Diabetes Care June 1990;13(6):610-630.
- 31. Schober E, Schoenle E, Van Dyk J, Wernicke-Panten K. Comparative Trial Between Insulin Glargine and NPH Insulin in Children and Adolescents With Type 1 Diabetes. Diabetes Care 2001; 24:2005-2006.
- 32. Skyler JS. Lessons from studies of insulin in pharmacokinetics. Diabetes Care 1986;9(6):666-667.
- 33. Unger RH, Grundy S. Hyperglycaemia as an inducer as well as a consequence of impaired islet cell function and insulin resistance: implications for the management of diabetes. Diabetologia March 1985;28(3):119-121