


Product Monograph - Lenalidomide
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| oral | Capsule, 2.5 mg, 5 mg, 7.5 mg, 10 mg, 15 mg, 25 mg | Lactose, Gelatin, Titanium dioxide, black imprinting ink. |
| oral | Capsule, 20 mg | Lactose, Gelatin, Titanium dioxide, FD&C Blue #1, Yellow Iron oxide, FD&C Yellow #6, black imprinting ink. |
INDICATIONS AND CLINICAL USE
- LENALIDOMIDE in combination with dexamethasone is indicated for the treatment of multiple myeloma patients who are not eligible for stem cell transplant.
Limitation of Use:
- LENALIDOMIDE is not indicated and is not recommended for the treatment of patients with chronic lymphocytic leukemia (CLL) outside of controlled clinical trials (see WARNINGS AND PRECAUTIONS, Increased Mortality in Patients with CLL).
Distribution restrictions
LENALIDOMIDE is only available through a controlled distribution program called NATLenAid. Under this program, only prescribers and pharmacists registered with the program are able to prescribe and dispense the product. In addition, LENALIDOMIDE can only be dispensed to patients who are registered and meet all the conditions of the NATLenAid program. Please call 1-800-296-9329 or log onto www.natcopharma.ca/natlenaid.
Geriatrics (> 65 years of age):
Lenalidomide has been used in clinical trials in subjects up to 95 years of age. The majority were ≥ 65 years of age. No effect of age on the clinical efficacy was observed in the Phase 3 clinical trials. Some differences in clinical safety have been identified between the elderly and younger subjects (see Special populations: Geriatrics > 65 years of age).
Because elderly patients are more likely to have decreased renal function, and lenalidomide is cleared by the kidney, starting dose adjustments based on stage of renal impairment and monitoring of renal function throughout treatment are recommended (see WARNINGS AND
PRECAUTIONS, Geriatrics and DOSAGE AND ADMINISTRATION, Starting Dose Adjustment for renal impairment).
Pediatrics (< 18 years of age):
The safety and effectiveness of lenalidomide in children and adolescents have not been established.
CONTRAINDICATIONS
̶ LENALIDOMIDE (lenalidomide) is contraindicated in patients who are hypersensitive to it or to thalidomide, pomalidomide or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING.
̶ LENALIDOMIDE is contraindicated in pregnant women and women at risk of becoming pregnant (see WARNINGS AND PRECAUTIONS). Lenalidomide is structurally related to thalidomide, a known human teratogen that causes severe and life-threatening birth defects. Lenalidomide induced malformations in monkeys similar to those described with thalidomide. If lenalidomide is taken during pregnancy, it may cause severe birth defects or death to the fetus (see WARNINGS AND PRECAUTIONS). Females of Child-Bearing Potential may be treated with LENALIDOMIDE provided that adequate contraception, with two simultaneous effective methods of contraception, is used to prevent fetal exposure to the drug. The choice of the two simultaneously effective contraceptive methods will necessitate a risk/benefit discussion between the patient and a qualified physician experienced in the use of contraceptive methods (see Serious Warnings and Precautions Box).
̶ Breast feeding women
̶ Male patients unable to follow or comply with the required contraceptive measures (see WARNINGS AND PRECAUTIONS, Special Populations – Male Patients).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions LENALIDOMIDE (lenalidomide) should be administered under the supervision of a qualified physician experienced in the use of cancer chemotherapeutic agents.
|
General
Patients should be informed to not give blood while taking LENALIDOMIDE and for 4 weeks after stopping LENALIDOMIDE. If a woman who is pregnant received their donated blood, her baby may be exposed to lenalidomide and may be born with birth defects.
In the treatment of previously treated multiple myeloma, consideration should be given to the dose of dexamethasone used in combination with LENALIDOMIDE (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Multiple Myeloma). This is based on safety data from a Phase 3 study conducted in 445 patients with newly diagnosed multiple myeloma including both transplant non-eligible, and transplant-eligible (newly diagnosed transplant-eligible is an unauthorized indication) patients. With a median follow up of 72.3 weeks, an increased mortality was observed in the lenalidomide / standard dose dexamethasone arm of 19.3% (43/223) compared to the lenalidomide /low dose dexamethasone arm of 6.8% (15/220). Considering that the patient population in the study included transplant eligible patients which differs from the authorized indication, these results should be interpreted with caution.
Cardiovascular
In the two Phase 3 previously treated multiple myeloma studies, use of lenalidomide was associated with an increased risk of cardiac disorders. The incidence of treatment emergent cardiac disorders was 18% and 11% in the lenalidomide /dexamethasone and
placebo/dexamethasone treatment groups, respectively. The rates of grade 3/4 cardiac events (9.1% versus 4.6%) and serious cardiac events (7.6% versus 3.4%) were higher in the lenalidomide /dexamethasone group as compared to the control group. Treatment with lenalidomide /dexamethasone resulted in a three-fold increase in the incidence of serious events of atrial fibrillation as compared with the placebo/dexamethasone.
In the Phase 3 transplant non-eligible newly diagnosed multiple myeloma (TNE NDMM) study, the incidence of treatment emergent cardiac disorders was 29.1%, 19.6%, and 23.8% in the lenalidomide / low dose dexamethasone given until progression (Rd), Rd for 18 cycles (Rd18) and melphalan/prednisone/thalidomide (MPT) Arms, respectively. The rates of grade 3/4 cardiac events were 11.8%, 7.2% and 8.5% and the rates of serious cardiac events were 13.2%, 9.4% and 8.1% in the Rd, Rd18 and MPT Arms, respectively (see ADVERSE REACTIONS, Clinical Trial Adverse Reactions).
Patients with risk factors for developing atrial fibrillation (e.g. existing heart disease, electrolyte abnormalities, hypertension and infections) should be closely monitored.
Venous and Arterial Thromboembolism
The combination of lenalidomide with dexamethasone is associated with an increased risk of venous thromboembolism (predominantly deep vein thrombosis (DVT) and pulmonary embolism (PE) and arterial thromboembolism (predominantly myocardial infarction and cerebrovascular events) in patients with MM. In previously treated multiple myeloma studies, which had varying use of antithrombotic prophylaxis, the number of patients experiencing a serious DVT event was higher in the lenalidomide /dexamethasone arm (7.1%; 25/353) as compared to those in the placebo/dexamethasone arm (3.1%; 11/350). In the TNE NDMM study in which nearly all patients received antithrombotic prophylaxis, the rate of serious DVT events was 3.6%, 2.0% and 1.5% in the Rd, Rd18 and MPT Arms, respectively. The rate of serious PE events was similar between the Rd, Rd18, and MPT Arms (3.8%, 2.8%, and 3.7%, respectively) (see ADVERSE REACTIONS).
Myocardial infarction has been reported in patients receiving lenalidomide, particularly in those with known risk factors and within the first 6 months of use. Consequently, patients with known risk factors should be closely monitored and action should be taken to minimize risk factors (e.g. smoking, hypertension, and hyperlipidemia).
Concomitant administration of erythropoietic agents or previous history of DVT may enhance the risk of thrombotic events. Therefore, erythropoietic agents, or other agents that may increase the risk of thrombosis, such as hormone replacement therapy and hormonal contraceptives, should be used with caution in patients receiving LENALIDOMIDE in combination with dexamethasone. Patients and physicians are advised to be observant for the signs and symptoms of thromboembolism. Physicians should make the decision when to discontinue therapy of erythropoietic or other agents that may increase the risk of thrombosis based on best clinical practice. Patients should be instructed to seek medical care if they develop symptoms such as a sudden shortness of breath, chest pain, arm or leg swelling. Prophylactic antithrombotic medications, such as low dose aspirin, low molecular weight heparins or warfarin, are recommended, especially in patients with additional thrombotic risk factors. The decision to take antithrombotic prophylactic measures should be made after careful assessment of an individual patient’s underlying risk factors.
Carcinogenesis and Mutagenesis
Carcinogenicity studies have not been conducted. Lenalidomide did not induce mutation in the Ames test, chromosome aberrations in cultured human peripheral blood lymphocytes, or mutation at the thymidine kinase (tk) locus of mouse lymphoma L5178Y cells. Lenalidomide did not increase morphological transformation in Syrian Hamster Embryo assay or induce micronuclei in the polychromatic erythrocytes of the bone marrow of male rats (see TOXICOLOGY).
- Second Primary Malignancies
An increase of second primary malignancies (SPM) has been observed in clinical trials in previously treated myeloma patients receiving lenalidomide/dexamethasone (3.98 per 100 person years) compared to controls (1.38 per 100 person years). Non invasive SPM comprise basal cell or squamous cell skin cancers. Most of the invasive SPMs were solid tumor malignancies.
In clinical trials of newly diagnosed multiple myeloma patients, an increase in invasive (hematologic primarily and solid tumor) SPM has been observed in those receiving lenalidomide.
In the clinical trials of newly diagnosed multiple myeloma patients not eligible for stem cell transplantation, a 4.4-fold increase in incidence rate of hematologic SPM (cases of AML) has been observed in patients receiving lenalidomide in combination with melphalan and prednisone (1.57 per 100 person-years) compared with melphalan in combination with prednisone (0.36 per 100 person-years). In patients receiving lenalidomide in combination with dexamethasone, the hematologic SPM incidence rate (0.14 per 100 person-years) was not increased as compared to thalidomide in combination with melphalan and prednisone (0.91 per 100 person-years).
In clinical trials of newly diagnosed multiple myeloma patients eligible for stem cell transplantation, an increased incidence rate of hematologic SPM has been observed in patients receiving lenalidomide as compared to placebo immediately following high-dose melphalan and autologous stem cell transplantation (ASCT) (1.27 to 1.56 versus 0.46 to 0.53 per 100 person-years, respectively). Cases of B-cell malignancies (including Hodgkin’s lymphoma) observed in the clinical trials were in patients who received lenalidomide in the post -ASCT setting.
The risk of occurrence of SPM must be taken into account before initiating treatment with LENALIDOMIDE. Physicians should carefully evaluate patients before and during treatment using standard cancer screening for occurrence of second primary malignancies and institute treatment as indicated.
Hematologic
Lenalidomide is associated with significant neutropenia and thrombocytopenia.
Patients should be advised to promptly report febrile episodes as a dose reduction may be required. In cases of thrombocytopenia, patients and physicians should be observant for signs and symptoms of bleeding, including petechiae and epistaxes.
- Multiple Myeloma
In previously treated multiple myeloma studies, Grade 3 and 4 hematologic toxicities including neutropenia (35.4%) and thrombocytopenia (13.0%) were more frequent in subjects treated with the combination of lenalidomide and dexamethasone than in subjects treated with dexamethasone alone. In the TNE NDMM study grade 3/4 neutropenia was reported in 27.8%, 26.5%, and 44.9% and grade 3/4 thrombocytopenia was reported in 8.3%, 8.0%, and 11.1% in the Rd, Rd18 and MPT Arms respectively (see ADVERSE REACTIONS).
Complete blood counts should be monitored at baseline, every 7 days (weekly) for the first 2 cycles (8 weeks), on days 1 and 15 of cycle 3, and every 28 days (4 weeks) thereafter (see Monitoring and Laboratory Tests).
Hepatic
Hepatic failure, including fatal cases, has occurred in patients treated with lenalidomide in combination with dexamethasone: acute hepatic failure, toxic hepatitis, cytolytic hepatitis, cholestatic hepatitis, and mixed cytolytic/cholestatic hepatitis have been reported (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions). The mechanism of severe drug-induced hepatotoxicity is unknown. Pre-existing viral liver disease, elevated baseline liver enzymes, and concomitant medications may be risk factors. Monitor liver enzymes periodically. Stop LENALIDOMIDE upon elevation of liver enzymes. After return to baseline values, treatment at a lower dose may be considered.
Immune
Angioedema, anaphylaxis and serious dermatologic reactions including Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) have been reported as rare cases, and drug reaction with eosinophilia and systemic symptoms (DRESS) has been reported as very rare, from post- marketing experience. DRESS may present with a cutaneous reaction (such as rash or exfoliative dermatitis), eosinophilia, fever, and/or lymphadenopathy with systemic complications such as hepatitis, nephritis, pneumonitis, myocarditis, and/or pericarditis. These events have the potential to be fatal. LENALIDOMIDE interruption or discontinuation should be considered for Grade 2-3 skin rash. LENALIDOMIDE must be discontinued for angioedema, anaphylaxis, skin rash Grade 4, exfoliative or bullous rash, or if SJS, TEN or DRESS is suspected, and should not be resumed following discontinuation from these reactions. Patients with a history of severe rash associated with thalidomide treatment should not receive lenalidomide (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment and ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Graft versus Host Disease
Graft versus host disease (GvHD) and other immune dysregulation reactions can be a common complication of hematopoietic cell transplants (HCT) and have been reported in post-transplant patients treated with lenalidomide. Some cases of acute GvHD were fatal, in particular with allogeneic hematopoietic cell transplantation (allo-HCT). The incidence of GvHD appears more frequent and serious when lenalidomide is given shortly (e.g. within 6 months) after allo-HCT. LENALIDOMIDE is not indicated as a maintenance therapy post HCT.
Solid Organ Transplant Rejection
Cases of solid organ transplant (SOT) rejection have been reported in the post-market setting with the use of lenalidomide and, in some cases, have resulted in a fatal outcome. Onset may be acute, occurring within 1 to 3 cycles of lenalidomide treatment. Potential contributing factors for SOT rejection in the reported cases include underlying disease (e.g., amyloidosis), concurrent infections and recent discontinuation or reduction of immunosuppressive therapy. The incidence rate of SOT rejection cannot be reliably estimated due to the limitation of post-marketing safety data and that patients with SOT were generally excluded from lenalidomide clinical trials. The benefit of treatment with LENALIDOMIDE versus the risk of possible SOT rejection should be considered in patients with a history of SOT before initiating LENALIDOMIDE therapy. Clinical and laboratory signs of SOT rejection should be closely monitored and LENALIDOMIDE therapy should be discontinued in the event of SOT rejection (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Infections
Viral Reactivation
Cases of viral reactivation have been reported in patients receiving lenalidomide, including serious cases of herpes zoster or hepatitis B virus (HBV) reactivation.
Some of the cases of viral reactivation had a fatal outcome.
Some of the cases of herpes zoster reactivation resulted in disseminated herpes zoster, meningitis herpes zoster or ophthalmic herpes zoster requiring a temporary hold or permanent discontinuation of the treatment with lenalidomide and adequate antiviral treatment.
Reactivation of hepatitis B virus (HBV) has been reported very rarely in lenalidomide treated patients who have previously been infected with HBV. Some of these cases progressed to acute hepatic failure and resulted in permanent discontinuation of lenalidomide or were fatal.
Caution should be exercised when LENALIDOMIDE is used in patients previously infected with HBV. These patients should be closely monitored for signs and symptoms of active HBV infection throughout therapy (See ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Progressive Multifocal Leukoencephalopathy
Cases of progressive multifocal leukoencephalopathy (PML), including fatal cases, have been reported with lenalidomide in combination with immunosuppressive therapy including dexamethasone. Physicians should consider PML in the differential diagnosis in patients with new or worsening neurological, cognitive or behavioural signs or symptoms and appropriate diagnostic measures for PML are recommended. If PML is suspected, further lenalidomide dosing must be suspended until PML has been excluded. If PML is confirmed, lenalidomide must be permanently discontinued.
Increased Mortality in Patients with CLL (non approved indication)
In a prospective randomized (1:1) clinical trial in the first line treatment of patients with chronic lymphocytic leukemia, single agent lenalidomide therapy increased the risk of death as compared to single agent chlorambucil. LENALIDOMIDE is not indicated and not recommended for use in CLL outside of controlled clinical trials.
Renal/Metabolic
Lenalidomide is primarily excreted unchanged by the kidney. Lower starting dose adjustment is recommended in patients with renal insufficiency in order to maintain an effective and safe level of LENALIDOMIDE. Based on a pharmacokinetic study in subjects with renal impairment due to a nonmalignant condition, a lenalidomide starting dose adjustment should be considered for patients with moderate or severe renal impairment and in patients on dialysis (patients with CrCL < 60 mL/min) (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency). There are no Phase III clinical trial experiences with End Stage Renal Disease (CrCL < 30 mL/min, requiring dialysis).
Patients with multiple myeloma, progressive disease and/or advanced age are more likely to have decreased renal function. The risk of serious renal disorders and renal failure may be greater in patients with impaired renal function. Periodic monitoring of renal function and dose adjustments are recommended based on stage of renal impairment.
Sensitivity/Resistance
Lenalidomide capsules contain lactose. Patients with rare hereditary problems of glucose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this product.
Thyroid Disorders
Both hypothyroidism and hyperthyroidism have been reported in patients treated with lenalidomide. Optimal control of co-morbid conditions that can affect thyroid function is recommended before start of LENALIDOMIDE treatment. Baseline and ongoing monitoring of thyroid function is recommended (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Tumor Lysis Syndrome
Tumor Lysis Syndrome (TLS) has been observed in patients with chronic lymphocytic leukemia (CLL), multiple myeloma (MM), and in non-Hodgkin’s Lymphoma [unauthorized indication] treated with lenalidomide. Some cases of TLS were fatal. Patients at risk for TLS are those with high tumor burden prior to treatment. Caution should be practiced when introducing these patients to LENALIDOMIDE. These patients should be monitored closely and appropriate precautions taken. Lenalidomide is not indicated and not recommended for use in CLL outside of controlled clinical trials.
Tumor Flare Reaction
Tumor flare reaction has occurred during investigational use of lenalidomide for CLL and mantle cell lymphoma (MCL) [unauthorized indication], and is characterized by tender lymph node swelling, low grade fever, pain and rash. LENALIDOMIDE is not indicated and not recommended for use in CLL outside of controlled clinical trials.
Tumor flare reaction may mimic progression of disease in patients with MCL. Monitoring and evaluation for tumor flare reaction is recommended in these patients.
Special Populations
- 1. Females of Child-Bearing Potential:
Females of Child-Bearing Potential are all females who are menstruating, amenorrheic from previous treatments, and/or perimenopausal.
Lenalidomide is an analogue of thalidomide, a known human teratogen that causes severe and life-threatening birth defects. An embryo-fetal development study in non-human primates indicates that lenalidomide produced malformations in the offspring of female monkeys given the drug during pregnancy, similar to birth defects observed in humans following exposure to thalidomide during pregnancy. The teratogenic effect of lenalidomide in humans cannot be ruled out. LENALIDOMIDE may cause fetal harm when administered to a pregnant female.
For Females of Child-Bearing Potential, LENALIDOMIDE is contraindicated unless ALL of the following conditions are met:
- The patient is capable of understanding and carrying out instructions. (In some cases, the patient will need a competent support person to ensure NATLenAid program compliance).
- The patient is willing and able to comply with the two mandatory, simultaneous and effective contraceptive measures or to commit to continually abstaining from heterosexual contact.
- The patient has a consultation with a health care professional, who has experience with the use of contraceptive methods, to discuss the best and most effective two simultaneous contraceptive methods to be used.
- The patient understands the cumulative risks of deep venous thrombosis, including, but not limited to, lenalidomide, dexamethasone, cancer and hormonal contraception.
- The patient knows the risk of possible contraceptive failure.
- The patient is willing and able to comply with the pregnancy testing requirements noted in detail below. This includes two negative pregnancy tests prior to the first dispense and on-going pregnancy tests throughout treatment.
- The patient is aware of the potential need for emergency contraception.
- The patient is informed of the risk of teratogenicity should a pregnancy occur.
- The patient knows and understands the need to consult her physician immediately if there is a risk of pregnancy.
- The patient acknowledges the importance of compliance with all the conditions of use.
Contraceptive Measures
All Females of Child-Bearing Potential (including those who normally do not use contraception due to a history of infertility, and those who have amenorrhea) must use the two simultaneous, effective methods of contraception:
- For at least 4 weeks before starting LENALIDOMIDE treatment.
- During dose interruptions.
- During LENALIDOMIDE treatment.
- For at least 4 weeks following the discontinuation of LENALIDOMIDE treatment.
- The patient who chooses to abstain from heterosexual contact as a contraceptive measure, must commit to using 2 methods of contraception at the same time if abstinence is no longer practiced.
- The use of hormonal contraceptives is associated with an increased risk of thromboembolic disorders. Hormonal contraceptives are not recommended (see WARNINGS AND PRECAUTIONS, Cardiovascular).
- Any method of contraception can fail. It is, therefore, critically important that Females of Child-Bearing Potential use two effective methods of contraception simultaneously.
- If pregnancy does occur during treatment, the drug should be immediately discontinued. Under these conditions, the patient should be referred to an obstetrician/gynecologist experienced in reproductive toxicity, for further evaluation and counseling.
- Any suspected embryo-fetal exposure to LENALIDOMIDE should be reported immediately by telephone to Natco at 1-800-296-9329.
- Female patients with a previous hysterectomy or bilateral oophorectomy are exempt from contraception use during lenalidomide therapy.
Pregnancy Testing:
- Females of Child-Bearing Potential must not be given LENALIDOMIDE until pregnancy is excluded. The patient must have two negative pregnancy tests before starting LENALIDOMIDE therapy, as well as subsequent tests throughout the treatment.
- The first pregnancy test should be conducted seven to 14 days prior to the start of therapy.
- The second pregnancy test should be conducted 24 hours prior to dispensing and starting the drug.
- A pregnancy test should be conducted weekly during the first month of treatment, monthly thereafter during treatment (or every two weeks if menses are irregular) and 4 weeks after the discontinuation of treatment.
- The pregnancy test should be a blood test performed in a licensed laboratory. The dates and results of pregnancy tests should be documented.
- The pregnancy test should have a serum hCG sensitivity of at least 25 mIU/ml.
Pregnancy testing and consultation with an obstetrician/gynecologist should also occur if a patient misses her period, or if there is any abnormal menstrual bleeding.
- 2. Pregnant Women:
- LENALIDOMIDE is contraindicated in females who are, or may become, pregnant.
- LENALIDOMIDE is contraindicated in Females of Child-Bearing Potential who are not using the two mandatory, simultaneous and effective methods of contraception or who are not continually abstaining from heterosexual sexual contact.
- If pregnancy does occur during treatment, the drug should be immediately discontinued. Under these conditions, the patient should be referred to an obstetrician/gynecologist experienced in reproductive toxicity, for further evaluation and counseling.
Any suspected embryo-fetal exposure to LENALIDOMIDE should be reported immediately by telephone to Natco at 1-800-296-9329.
- 3. Nursing Women:
LENALIDOMIDE should not be used when a patient is breast-feeding (See CONTR
AINDICATIONS).
The safe use of lenalidomide during lactation has not been established.
- 4. Male Patients:
Lenalidomide is present in the semen of males who take lenalidomide (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Distribution). There is a potential risk of birth defects, still births and spontaneous abortions if a developing fetus is exposed to lenalidomide through the semen of male patients (see WARNINGS AND PRECAUTIONS, Females of Child-Bearing Potential). Therefore, males receiving LENALIDOMIDE must always use a condom during any sexual contact with Females of Child-Bearing Potential even if they have undergone a successful vasectomy. The condom should be used:
- While the Male Patient is taking LENALIDOMIDE.
- During interruption of treatment.
- For at least 4 weeks after stopping LENALIDOMIDE.
Patients should not donate semen while taking LENALIDOMIDE and for at least 4 weeks after stopping LENALIDOMIDE.
Male patients must inform their female sexual partners of child-bearing potential that:
- The male patient is taking LENALIDOMIDE.
- There is a potential risk of birth defects, stillbirths and spontaneous abortions if a developing fetus is exposed to the semen of the male patient.
- A condom must be used during any sexual contact.
If a pregnancy occurs in a partner of a male patient taking lenalidomide, it is recommended to refer the female partner to a physician specialized or experienced in teratology for evaluation and advice.
- 5. Pediatrics (< 18 years of age):
Safety and effectiveness in pediatric patients below the age of 18 have not been established. In the clinical trial program, no patients under 18 years of age were treated. For ALL sexually active Females of Child-Bearing Potential the use of two simultaneous effective methods of contraception is mandatory.
- 6. Geriatrics (> 65 years of age):
Elderly patients are more likely to have decreased renal function, and the risk of adverse reactions to lenalidomide may be greater in patients with impaired renal function. Based on stage of renal impairment, lower LENALIDOMIDE starting doses are recommended (see Renal/Metabolic and DOSAGE AND ADMINISTRATION, Starting Dose Adjustment for Renal Impairment).
For transplant non-eligible newly diagnosed multiple myeloma patients the concomitant dexamethasone dose should be reduced by half in patients > 75 years of age (see DOSAGE AND ADMINISTRATION).
- Multiple Myeloma
In the clinical trial for transplant non-eligible newly diagnosed multiple myeloma patients, lenalidomide in combination with dexamethasone has been used in patients up to age 91. The percentage of patients ≥ 65 years of age was similar across treatment arms (94-95%) as was the percentage of patients over the age of 75 years of age (34-36%). Overall, across all treatment arms, the frequency in most of the AE categories (e.g., all AEs, grade 3/4 AEs, serious AEs) was higher in older (>75 years of age) than in younger (≤ 75 years of age) patients. Grade 3 or 4 TEAEs in the General Disorders and Administration Site Conditions SOC were reported at a higher frequency (with a difference of at least 5%) in older patients than in younger patients across all treatment arms. Grade 3 or 4 TEAEs in the Infections and Infestations, Cardiac
Disorders (including cardiac failure and congestive heart failure), Skin and Subcutaneous Tissue Disorders, and Renal and Urinary Disorders (including renal failure) SOC were also reported slightly, but consistently, more frequently (< 5% difference), in older patients than in younger patients across all treatment arms.
In the clinical trials for previously treated multiple myeloma, lenalidomide in combination with dexamethasone was used in patients up to 86 years of age. In the lenalidomide /dexamethasone arm (n=353), patients > 65 years of age were more likely than patients ≤ 65 years of age to experience serious events of cardiac disorders (15.8% versus 4.3%), including atrial fibrillation (6.8% versus 1.9%) as well as diarrhea (4.1% vs. 2.4%), fatigue (9.6% vs. 4.3%), pulmonary embolism (6.2% vs. 2.4%), and syncope (3.4% vs. 2.4%).
Monitoring and Laboratory Tests
Complete blood cell count (CBC), including white blood cell count with differential, hemoglobin, platelets, blood chemistries including SGOT/AST, SGPT/ALT, direct bilirubin, creatinine, and creatinine clearance (CrCL) should be monitored at baseline and throughout treatment with LENALIDOMIDE. Cases of hypothyroidism and hyperthyroidism have been reported with lenalidomide. Optimal control of thyroid function is recommended before start of treatment. Baseline and ongoing monitoring of thyroid function is recommended.
Twelve (12) lead ECGs were mandatory in pivotal studies. Patients with irregularly irregular heart rates at the time of follow-up should receive an additional ECG and evaluation for atrial fibrillation. If atrial fibrillation is detected, the patient should be treated in accordance with current medical practice in order to prevent potentially serious consequences.
The risk of occurrence of SPM must be taken into account before initiating treatment with LENALIDOMIDE. Physicians should carefully evaluate patients before and during treatment using standard cancer screening for occurrence of second primary malignancies and institute treatment as indicated.
- Multiple Myeloma
For multiple myeloma patients, monitor complete blood count with differential, platelet count, hemoglobin, and hematocrit every 7 days (weekly) for the first 2 cycles (8 weeks), on days 1 and 15 of cycle 3, and every 28 days (4 weeks) thereafter of LENALIDOMIDE treatment or when deemed necessary for cytopenias.
Geriatric patients should be closely monitored for cardiac and renal function.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Phase 3 Randomized Open-Label Study in Transplant Non-Eligible Newly Diagnosed Multiple Myeloma Patients
Data were evaluated from 1613 patients in a phase 3, randomized, open-label study who received at least one dose of lenalidomide with low dose dexamethasone (Rd) given for 2 different durations of time (i.e., until disease progression [Arm Rd; N=532] or for up to eighteen 28-day cycles [Arm Rd18; N=540]), or who received melphalan, prednisone, and thalidomide (Arm MPT; N=541) for a maximum of twelve 42-day cycles (72 weeks). The median duration of treatment differed between treatment groups and should be taken into consideration when comparing frequencies of adverse events across treatment groups. The median duration of treatment was 80.2 weeks (range 0.7-246.7) in the Arm Rd, 72 weeks (range 0.9-102.6) in the Arm Rd18, and 67.1 weeks (range 0.1 – 110.0) in the Arm MPT.
The most frequently reported adverse events were comparable in the Arm Rd and Arm Rd18, and included: diarrhea, anemia, constipation, peripheral edema, neutropenia, fatigue, back pain, nausea, asthenia, and insomnia. The most frequently reported Grade 3 or 4 events included: neutropenia, anemia, thrombocytopenia, pneumonia, asthenia, fatigue, back pain, hypokalemia, rash, cataract, lymphopenia, dyspnea, DVT, and hyperglycemia.
Infections overall were reported more frequently in Arm Rd (74.8%) compared to Arm MPT (56.4%). Grade 3 - 4 infections, and serious infections respectively, were reported more frequently in Arm Rd (28.9%, 30.6%) than Arm MPT (17.2%, 16.5%).
In the Arm Rd, the most common adverse events leading to dose interruption of lenalidomide were neutropenia (21.8%), pneumonia (7.5%), and rash (6.6%); overall the median time to the first dose interruption of lenalidomide was 7 weeks. The most common adverse events leading to dose reduction of lenalidomide in the Arm Rd were neutropenia (7.5%), rash (4.5%), fatigue (3.6%), and diarrhea (3.2%); overall the median time to the first dose reduction of lenalidomide was 16 weeks. In Arm Rd, the most common adverse events leading to discontinuation of lenalidomide were infection events (3.4%).
Multiple myeloma was the most common cause of death across all three treatment arms during the study (active treatment and follow-up phases). For the lenalidomide arms, during the active treatment phase, the most common cause of death was infections (3.8%, 2.0% and 1.8% in Arms Rd, Rd18 and MPT respectively), followed by cardiac disorders (1.9%, 1.7% and 0.7% in Arms Rd, Rd18 and MPT respectively).
In both Arm Rd and Rd18, the frequencies of onset of adverse events were generally highest in the first 6 months of treatment and then the frequencies decreased over time or remained stable throughout treatment, except for cataracts. The frequency of onset of cataracts increased over time with 0.7% incidence during the first 6 months and up to 9.6% by the 2nd year of treatment with Rd.
With regard to age, the frequency in most of the AE categories (e.g., all AEs, grade 3/4 AEs, serious AEs) was higher in older (>75 years of age) than in younger (≤ 75 years of age) patients (see WARNINGS AND PRECAUTIONS Special Populations Geriatrics).
Treatment emergent adverse events observed in patients treated with Rd and Rd18 are listed in Table 1 by system organ class and frequency for all adverse events ≥ 5% and/or for Grade 3 or 4 events ≥ 1%.
Table 1: Summary of Adverse Events Reported in ≥ 5% and Grade 3-4 Adverse
Events in ≥ 1% of the Rd and Rd18 treated patients in the Transplant Non-Eligible
Newly Diagnosed Multiple Myeloma Study
| System organ class / Preferred terma | Rd (N=532) | Rd18 (N=540) | MPT (N=541) | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | ||||||||||||
| General Disorders & Administration Site Conditions | 437 (82.1) | 132 (24.8) | 430 (79.6) | 126 (23.3) | 422 (78.0) | 106 (19.6) | |||||||||||
| Edema peripheral | 211 (39.7) | 18 (3.4) | 169 (31.3) | 10 (1.9) | 215 (39.7) | 16 (3.0) | |||||||||||
| Fatigue | 173 (32.5) | 39 (7.3) | 177 (32.8) | 46 (8.5) | 154 (28.5) | 31 (5.7) | |||||||||||
| Asthenia | 150 (28.2) | 41 (7.7) | 123 (22.8) | 33 (6.1) | 124 (22.9) | 32 (5.9) | |||||||||||
| Pyrexia | 114 (21.4) | 13 (2.4) | 102 (18.9) | 7 (1.3) | 76 (14.0) | 7 (1.3) | |||||||||||
| Edema | 38 (7.1) | 5 (0.9) | 28 (5.2) | 0 (0.0) | 32 (5.9) | 4 (0.7) | |||||||||||
| Non-cardiac chest pain | 29 (5.5) | 2 (0.4) | 31 (5.7) | 4 (0.7) | 18 (3.3) | 1 (0.2) | |||||||||||
| General physical health deterioration | 23 (4.3) | 16 (3.0) | 24 (4.4) | 16 (3.0) | 16 (3.0) | 12 (2.2) | |||||||||||
| Gastrointestinal Disorders | 434 (81.6) | 75 (14.1) | 411 (76.1) | 58 (10.7) | 412 (76.2) | 67 (12.4) | |||||||||||
| Diarrhea | 242 (45.5) | 21 (3.9) | 208 (38.5) | 18 (3.3) | 89 (16.5) | 8 (1.5) | |||||||||||
| Constipation | 229 (43.0) | 12 (2.3) | 212 (39.3) | 10 (1.9) | 285 (52.7) | 29 (5.4) | |||||||||||
| Nausea | 152 (28.6) | 5 (0.9) | 128 (23.7) | 4 (0.7) | 165 (30.5) | 13 (2.4) | |||||||||||
| Vomiting | 93 (17.5) | 4 (0.8) | 68 (12.6) | 2 (0.4) | 109 (20.1) | 10 (1.8) | |||||||||||
| Abdominal pain | 69 (13.0) | 7 (1.3) | 41 (7.6) | 6 (1.1) | 30 (5.5) | 3 (0.6) | |||||||||||
| Dyspepsia | 57 (10.7) | 2 (0.4) | 28 (5.2) | 1 (0.2) | 36 (6.7) | 0 (0.0) | |||||||||||
| Abdominal pain upper | 45 (8.5) | 0 (0.0) | 37 (6.9) | 2 (0.4) | 29 (5.4) | 0 (0.0) | |||||||||||
| Dry mouth | 37 (7.0) | 0 (0.0) | 38 (7.0) | 0 (0.0) | 62 (11.5) | 1 (0.2) | |||||||||||
| Musculoskeletal & Connective Tissue Disorders | 408 (76.7) | 102 (19.2) | 367 (68.0) | 91 (16.9) | 311 (57.5) | 77 (14.2) | |||||||||||
| Back pain | 170 (32.0) | 37 (7.0) | 145 (26.9) | 34 (6.3) | 116 (21.4) | 28 (5.2) | |||||||||||
| Muscles spasms | 109 (20.5) | 3 (0.6) | 102 (18.9) | 3 (0.6) | 61 (11.3) | 4 (0.7) | |||||||||||
| Arthralgia | 101 (19.0) | 9 (1.7) | 71 (13.1) | 8 (1.5) | 66 (12.2) | 8 (1.5) | |||||||||||
| Bone pain | 87 (16.4) | 16 (3.0) | 77 (14.3) | 15 (2.8) | 62 (11.5) | 14 (2.6) | |||||||||||
| Pain in extremity | 79 (14.8) | 8 (1.5) | 66 (12.2) | 8 (1.5) | 61 (11.3) | 7 (1.3) | |||||||||||
| System organ class / Preferred terma | Rd (N=532) | Rd18 (N=540) | MPT (N=541) |
|---|
All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | |
|---|---|---|---|---|---|---|
| Musculoskeletal pain | 67 (12.6) | 2 (0.4) | 59 (10.9) | 5 (0.9) | 36 (6.7) | 2 (0.4) |
| Musculoskeletal chest pain | 60 (11.3) | 6 (1.1) | 51 (9.4) | 5 (0.9) | 39 (7.2) | 3 (0.6) |
| Muscular weakness | 43 (8.1) | 5 (0.9) | 35 (6.5) | 8 (1.5) | 29 (5.4) | 5 (0.9) |
| Neck pain | 40 (7.5) | 3 (0.6) | 19 (3.5) | 1 (0.2) | 10 (1.8) | 1 (0.2) |
| Myalgia | 27 (5.1) | 1 (0.2) | 19 (3.5) | 1 (0.2) | 17 (3.1) | 0 (0.0) |
| Infections & Infestations | 398 (74.8) | 154 (28.9) | 377 (69.8) | 118 (21.9) | 305 (56.4) | 93 (17.2) |
| Bronchitis | 90 (16.9) | 9 (1.7) | 59 (10.9) | 6 (1.1) | 43 (7.9) | 3 (0.6) |
| Nasopharyngitis | 80 (15.0) | 0 (0.0) | 54 (10.0) | 0 (0.0) | 33 (6.1) | 0 (0.0) |
| Urinary tract infection | 76 (14.3) | 8 (1.5) | 63 (11.7) | 8 (1.5) | 41 (7.6) | 3 (0.6) |
| Upper respiratory tract infection | 69 (13.0) | 3 (0.6) | 53 (9.8) | 8 (1.5) | 31 (5.7) | 3 (0.6) |
| Pneumonia | 66 (12.4) | 43 (8.1) | 68 (12.6) | 45 (8.3) | 40 (7.4) | 31 (5.7) |
| Respiratory tract infection | 35 (6.6) | 7 (1.3) | 25 (4.6) | 4 (0.7) | 21 (3.9) | 1 (0.2) |
| Influenza | 33 (6.2) | 5 (0.9) | 23 (4.3) | 4 (0.7) | 15 (2.8) | 0 (0.0) |
| Gastroenteritis | 32 (6.0) | 0 (0.0) | 17 (3.1) | 1 (0.2) | 13 (2.4) | 2 (0.4) |
| Lower respiratory tract infection | 29 (5.5) | 10 (1.9) | 14 (2.6) | 3 (0.6) | 16 (3.0) | 3 (0.6) |
| Rhinitis | 29 (5.5) | 0 (0.0) | 24 (4.4) | 0 (0.0) | 14 (2.6) | 0 (0.0) |
| Cellulitis | 22 (4.1) | 8 (1.5) | 16 (3.0) | 3 (0.6) | 6 (1.1) | 2 (0.4) |
| Sepsis | 17 (3.2) | 14 (2.6) | 10 (1.9) | 8 (1.5) | 9 (1.7) | 7 (1.3) |
| Nervous System Disorders | 371 (69.7) | 85 (16.0) | 333 (61.7) | 58 (10.7) | 429 (79.3) | 164 (30.3) |
| Peripheral sensory neuropathy | 109 (20.5) | 6 (1.1) | 92 (17.0) | 2 (0.4) | 191 (35.3) | 51 (9.4) |
| Paraesthesia | 85 (16.0) | 0 (0.0) | 74 (13.7) | 0 (0.0) | 103 (19.0) | 14 (2.6) |
| Dizziness | 84 (15.8) | 4 (0.8) | 70 (13.0) | 4 (0.7) | 114 (21.1) | 16 (3.0) |
| Headache | 75 (14.1) | 3 (0.6) | 52 (9.6) | 2 (0.4) | 56 (10.4) | 5 (0.9) |
| Tremor | 75 (14.1) | 5 (0.9) | 73 (13.5) | 4 (0.7) | 100 (18.5) | 9 (1.7) |
| Hypoaesthesia | 44 (8.3) | 0 (0.0) | 24 (4.4) | 3 (0.6) | 41 (7.6) | 4 (0.7) |
| Dysgeusia | 39 (7.3) | 1 (0.2) | 45 (8.3) | 0 (0.0) | 22 (4.1) | 1 (0.2) |
| Neuropathy peripheral | 34 (6.4) | 12 (2.3) | 22 (4.1) | 5 (0.9) | 62 (11.5) | 21 (3.9) |
| Somnolence | 31 (5.8) | 4 (0.8) | 21 (3.9) | 1 (0.2) | 51 (9.4) | 7 (1.3) |
| Peripheral motor neuropathy | 25 (4.7) | 7 (1.3) | 15 (2.8) | 5 (0.9) | 27 (5.0) | 9 (1.7) |
| Syncope | 22 (4.1) | 10 (1.9) | 17 (3.1) | 8 (1.5) | 27 (5.0) | 21 (3.9) |
| Blood & Lymphatic System Disorders | 346 (65.0) | 224 (42.1) | 325 (60.2) | 214 (39.6) | 423 (78.2) | 315 (58.2) |
| Anemia | 233 (43.8) | 97 (18.2) | 193 (35.7) | 85 (15.7) | 229 (42.3) | 102 (18.9) |
| Neutropenia | 186 (35.0) | 148 (27.8) | 178 (33.0) | 143 (26.5) | 328 (60.6) | 243 (44.9) |
| Thrombocytopenia | 104 (19.5) | 44 (8.3) | 100 (18.5) | 43 (8.0) | 135 (25.0) | 60 (11.1) |
| Leukopenia | 63 (11.8) | 24 (4.5) | 60 (11.1) | 30 (5.6) | 94 (17.4) | 53 (9.8) |
| System organ class / Preferred terma | Rd (N=532) | Rd18 (N=540) | MPT (N=541) |
|---|
All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | |
|---|---|---|---|---|---|---|
| Lymphopenia | 59 (11.1) | 30 (5.6) | 43 (8.0) | 18 (3.3) | 71 (13.1) | 37 (6.8) |
| Febrile Neutropenia | 7 (1.3) | 6 (1.1) | 17 (3.1) | 16 (3.0) | 15 (2.8) | 14 (2.6) |
| Pancytopenia | 5 (0.9) | 1 (0.2) | 6 (1.1) | 3 (0.6) | 7 (1.3) | 5 (0.9) |
| Respiratory, Thoracic & Mediastinal Disorders | 306 (57.5) | 87 (16.4) | 259 (48) | 53 (9.8) | 246 (45.5) | 54 (10.0) |
| Cough | 121 (22.7) | 4 (0.8) | 94 (17.4) | 1 (0.2) | 68 (12.6) | 3 (0.6) |
| Dyspnoea | 117 (22.0) | 30 (5.6) | 89 (16.5) | 22 (4.1) | 113 (20.9) | 18 (3.3) |
| Productive cough | 33 (6.2) | 2 (0.4) | 24 (4.4) | 0 (0.0) | 16 (3.0) | 0 (0.0) |
| Epistaxis | 32 (6.0) | 2 (0.4) | 31 (5.7) | 2 (0.4) | 17 (3.1) | 0 (0.0) |
| Dysphonia | 30 (5.6) | 0 (0.0) | 22 (4.1) | 0 (0.0) | 9 (1.7) | 0 (0.0) |
| Oropharyngeal pain | 30 (5.6) | 0 (0.0) | 22 (4.1) | 0 (0.0) | 14 (2.6) | 0 (0.0) |
| Dyspnoea exertional | 27 (5.1) | 6 (1.1) | 29 (5.4) | 2 (0.4) | 23 (4.3) | 0 (0.0) |
| Pulmonary embolism | 21 (3.9) | 20 (3.8) | 18 (3.3) | 16 (3.0) | 23 (4.3) | 20 (3.7) |
| Pulmonary edema | 15 (2.8) | 8 (1.5) | 4 (0.7) | 0 (0.0) | 6 (1.1) | 4 (0.7) |
| Chronic obstructive pulmonary disease | 11 (2.1) | 11 (2.1) | 8 (1.5) | 4 (0.7) | 3 (0.6) | 2 (0.4) |
| Respiratory failure | 9 (1.7) | 8 (1.5) | 7 (1.3) | 4 (0.7) | 5 (0.9) | 3 (0.6) |
| Metabolism & Nutritional Disorders | 298 (56.0) | 120 (22.6) | 274 (50.7) | 87 (16.1) | 192 (35.5) | 62 (11.5) |
| Decreased appetite | 123 (23.1) | 14 (2.6) | 115 (21.3) | 7 (1.3) | 72 (13.3) | 5 (0.9) |
| Hypokalemia | 91 (17.1) | 35 (6.6) | 62 (11.5) | 20 (3.7) | 38 (7.0) | 11 (2.0) |
| Hyperglycemia | 62 (11.7) | 28 (5.3) | 52 (9.6) | 23 (4.3) | 19 (3.5) | 9 (1.7) |
| Hypocalcaemia | 57 (10.7) | 23 (4.3) | 56 (10.4) | 19 (3.5) | 31 (5.7) | 8 (1.5) |
| Dehydration | 25 (4.7) | 8 (1.5) | 29 (5.4) | 13 (2.4) | 17 (3.1) | 9 (1.7) |
| Gout | 18 (3.4) | 8 (1.5) | 13 (2.4) | 0 (0.0) | 9 (1.7) | 0 (0.0) |
| Diabetes mellitus | 15 (2.8) | 8 (1.5) | 8 (1.5) | 4 (0.7) | 4 (0.7) | 2 (0.4) |
| Hypophosphatemia | 15 (2.8) | 7 (1.3) | 10 (1.9) | 3 (0.6) | 1 (0.2) | 1 (0.2) |
| Hyponatremia | 13 (2.4) | 7 (1.3) | 15 (2.8) | 13 (2.4) | 11 (2.0) | 6 (1.1) |
| Skin & Subcutaneous Tissue Disorders | 285 (53.6) | 52 (9.8) | 276 (51.1) | 47 (8.7) | 217 (40.1) | 38 (7.0) |
| Rash | 114 (21.4) | 33 (6.2) | 131 (24.3) | 28 (5.2) | 93 (17.2) | 28 (5.2) |
| Pruritus | 47 (8.8) | 2 (0.4) | 49 (9.1) | 2 (0.4) | 24 (4.4) | 2 (0.4) |
| Erythema | 33 (6.2) | 0 (0.0) | 27 (5.0) | 0 (0.0) | 18 (3.3) | 0 (0.0) |
| Dry skin | 30 (5.6) | 1 (0.2) | 30 (5.6) | 0 (0.0) | 36 (6.7) | 0 (0.0) |
| Psychiatric Disorders | 255 (47.9) | 37 (7.0) | 234 (43.3) | 34 (6.3) | 167 (30.9) | 14 (2.6) |
| Insomnia | 147 (27.6) | 4 (0.8) | 127 (23.5) | 6 (1.1) | 53 (9.8) | 0 (0.0) |
| Depression | 58 (10.9) | 10 (1.9) | 46 (8.5) | 4 (0.7) | 30 (5.5) | 1 (0.2) |
| Anxiety | 41 (7.7) | 2 (0.4) | 36 (6.7) | 2 (0.4) | 41 (7.6) | 2 (0.4) |
| Confusional state | 38 (7.1) | 14 (2.6) | 29 (5.4) | 11 (2.0) | 25 (4.6) | 4 (0.7) |
| Vascular Disorders | 189 (35.5) | 58 (10.9) | 148 (27.4) | 35 (6.5) | 138 (25.5) | 35 (6.5) |
| System organ class / Preferred terma | Rd (N=532) | Rd18 (N=540) | MPT (N=541) |
|---|
All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | All gradesb n (% ) | Gradeb 3-4 n (% ) | |
|---|---|---|---|---|---|---|
| Deep vein thrombosis | 54 (10.2) | 29 (5.5) | 36 (6.7) | 20 (3.7) | 20 (3.7) | 14 (2.6) |
| Hypotension | 51 (9.6) | 11 (2.1) | 35 (6.5) | 8 (1.5) | 36 (6.7) | 6 (1.1) |
| Hypertension | 37 (7.0) | 7 (1.3) | 27 (5.0) | 2 (0.4) | 36 (6.7) | 6 (1.1) |
| Injury Poisoning & Procedural Complications | 180 (33.8) | 43 (8.1) | 127 (23.5) | 29 (5.4) | 126 (23.3) | 30 (5.5) |
| Fall | 43 (8.1) | 5 (0.9) | 25 (4.6) | 6 (1.1) | 25 (4.6) | 6 (1.1) |
| Contusion | 33 (6.2) | 1 (0.2) | 24 (4.4) | 1 (0.2) | 15 (2.8) | 0 (0.0) |
| Spinal compression fracture | 19 (3.6) | 8 (1.5) | 10 (1.9) | 1 (0.2) | 15 (2.8) | 6 (1.1) |
| Eye Disorders | 171 (32.1) | 45 (8.5) | 126 (23.3) | 22 (4.1) | 86 (15.9) | 7 (1.3) |
| Cataract | 73 (13.7) | 31 (5.8) | 31 (5.7) | 14 (2.6) | 5 (0.9) | 3 (0.6) |
| Vision blurred | 29 (5.5) | 1 (0.2) | 20 (3.7) | 2 (0.4) | 24 (4.4) | 2 (0.4) |
| Cataract subcapsular | 11 (2.1) | 7 (1.3) | 2 (0.4) | 0 (0.0) | 0 (0.0) | 0 (0.0) |
| Investigations | 169 (31.8) | 47 (8.8) | 173 (32.0) | 36 (6.7) | 141 (26.1) | 30 (5.5) |
| Weight decreased | 72 (13.5) | 11 (2.1) | 78 (14.4) | 4 (0.7) | 48 (8.9) | 4 (0.7) |
| Blood creatinine increased | 35 (6.6) | 8 (1.5) | 25 (4.6) | 5 (0.9) | 24 (4.4) | 6 (1.1) |
| Cardiac Disorders | 155 (29.1) | 63 (11.8) | 106 (19.6) | 39 (7.2) | 129 (23.8) | 46 (8.5) |
| Atrial fibrillation | 37 (7.0) | 13 (2.4) | 25 (4.6) | 9 (1.7) | 25 (4.6) | 6 (1.1) |
| Cardiac failure | 17 (3.2) | 10 (1.9) | 16 (3.0) | 8 (1.5) | 14 (2.6) | 9 (1.7) |
| Cardiac failure congestive | 14 (2.6) | 8 (1.5) | 7 (1.3) | 6 (1.1) | 9 (1.7) | 6 (1.1) |
| Acute myocardial infarction | 6 (1.1) | 6 (1.1) | 1 (0.2) | 1 (0.2) | 4 (0.7) | 4 (0.7) |
| Renal & Urinary Disorders | 145 (27.3) | 46 (8.6) | 108 (20.0) | 39 (7.2) | 88 (16.3) | 39 (7.2) |
| Renal failure | 28 (5.3) | 12 (2.3) | 33 (6.1) | 18 (3.3) | 22 (4.1) | 16 (3.0) |
| Renal failure acute | 23 (4.3) | 18 (3.4) | 22 (4.1) | 16 (3.0) | 15 (2.8) | 13 (2.4) |
| Renal impairment | 15 (2.8) | 6 (1.1) | 6 (1.1) | 0 (0.0) | 7 (1.3) | 2 (0.4) |
| Ear & Labyrinth Disorders | 58 (10.9) | 3 (0.6) | 45 (8.3) | 2 (0.4) | 77 (14.2) | 4 (0.7) |
| Vertigo | 27 (5.1) | 2 (0.4) | 20 (3.7) | 1 (0.2) | 35 (6.5) | 1 (0.2) |
| Neoplasms Benign, Malignant & Unspecified (Including Cysts & Polyps) | 54 (10.2) | 26 (4.9) | 42 (7.8) | 26 (4.8) | 22 (4.1) | 9 (1.7) |
| Squamous cell carcinoma of skin | 14 (2.6) | 8 (1.5) | 5 (0.9) | 4 (0.7) | 1 (0.2) | 0 (0.0) |
aSystem Organ Class and Preferred Terms are coded using the MedDRA dictionary version 15.1
bSeverity Grades are based on US National Cancer Institute Common Toxicity Criteria version 3.0 d = low-dose dexamethasone; M = melphalan; P = prednisone; R = lenalidomide; T = thalidomide When an adverse event was reported multiple times within a given preferred term, only one event with the worst severity was counted per subject. Data cutoff date = 24 May 2013.
In the study of patients with transplant non-eligible newly diagnosed multiple myeloma the following serious adverse events (considered related to study drug treatment) were reported in ≥ 1% of Rd and /or Rd18 treated patients:
Blood and Lymphatic System Disorders: anemia, neutropenia, febrile neutropenia
Cardiac Disorders: atrial fibrillation
General Disorders and Administration Site Conditions: general physical health deterioration
Infections and Infestations: pneumonia, sepsis
Neoplasms Benign, Malignant and Unspecified (including cysts and polyps): squamous cell carcinoma of skin
Respiratory, Thoracic and Mediastinal Disorders: pulmonary embolism
Vascular Disorders: deep vein thrombosis
Phase 3 Randomized Double Blind Placebo-Controlled Studies in Previously Treated Multiple Myeloma Patients
Data were evaluated from 703 patients who received at least one dose of lenalidomide/dexamethasone (353 patients) or placebo/dexamethasone (350 patients). Overall, the adverse event data demonstrate that the addition of lenalidomide to dexamethasone was accomplished with only a minimal increase in toxicity. The incidences of lethargy, neutropenia, thrombocytopenia, anemia NOS, leukopenia NOS, lymphopenia, diarrhea NOS, constipation, dry mouth, rash NOS, dry skin, tremor, dizziness, dysgeusia, muscle cramp, back pain, dyspnea NOS, nasopharyngitis, pharyngitis, upper respiratory tract infection NOS, pneumonia NOS, anorexia, hypokalemia, hypocalcemia, hypomagnesemia, vision blurred, and DVT were higher in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group.
Based on pooled data from two studies, all subjects experienced at least one adverse event when on lenalidomide/dexamethasone combination treatment. A greater proportion of patients in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group had grade 3/4 (83.3% vs. 69.7%) and serious (57.2% vs. 46.6%) adverse events. More patients taking lenalidomide/dexamethasone had experienced an adverse event leading to dose reduction/interruption (76.5% vs. 57.7%) and drug discontinuation (24.9% vs. 18.0%). The incidences of serious cardiac and DVT events were 7.6% and 7.1% in the lenalidomide/dexamethasone group as compared to 3.4% and 3.1% in the placebo/dexamethasone group, respectively (see WARNINGS AND PRECAUTIONS).
Treatment-emergent cardiac disorders of any kind were reported more frequently among subjects treated with lenalidomide/dexamethasone (18.1%; 64/353) than in subjects treated with placebo/dexamethasone (11.1%, 39/350). A total of 33 serious cardiac events were reported in 27 lenalidomide/dexamethasone subjects compared to 15 events in 12 placebo/dexamethasone subjects. Serious cardiac disorders included atrial fibrillation (12 vs. 2 subjects), cardiac failure congestive (5 vs. 0 subjects), acute myocardial infarction (3 vs. 0 subjects), coronary artery disease (3 vs. 0 subjects), atrial flutter (2 vs. 0 subjects), arteriospasm coronary (1 vs. 0 subjects), acute coronary syndrome (1 vs. 0 subjects), and pulmonary edema NOS (1 vs 4 subjects). For serious events of atrial fibrillation, the exposure adjusted incidence density was three-fold higher for the lenalidomide/dexamethasone group than for the placebo/dexamethasone group (0.033 versus 0.010 events per person per year). If atrial fibrillation is detected, the patient should be treated in accordance with current medical practice in order to prevent potentially serious consequences.
Cardiac adverse events leading to the discontinuation of study medication were atrial fibrillation (2/353) and acute myocardial infarction (2/353) in the lenalidomide /dexamethasone arm; and pulmonary edema NOS (3/350) in the placebo/dexamethasone arm.
Approximately 39% of subjects in the lenalidomide /dexamethasone group required a reduction in their lenalidomide dose, and approximately 31% of subjects required a reduction in their dexamethasone dose. Approximately 11% of subjects in the placebo/dexamethasone group required a reduction in their placebo dose and approximately 16% required a reduction in their dexamethasone dose.
Ten deaths were considered to be lenalidomide/dexamethasone related: 3 due to cerebrovascular accident, 1 due to pneumonia, 1 due to leukoencephalopathy, 1 due to pulmonary embolism, 1 due to cardiac arrest, 1 due to pneumonia NOS/respiratory failure, 1 due to pancytopenia/pneumonia NOS/sepsis NOS and 1 due to sudden death of unknown causes.
Four deaths were considered placebo/dexamethasone related: 1 due to brain edema/pulmonary edema NOS, 1 due to pulmonary edema NOS, 1 due to pneumonia NOS, and 1 of unknown cause.
One case of hypersensitivity pneumonitis-like syndrome was reported with lenalidomide use. The patient was dosed with lenalidomide in cycles of 25 mg/d on days 1 to 21, followed by 7 days off. Dexamethasone was cycled at 40 mg/d on days 1–4, 9–12, and 17–20, followed by 7 days off. Treatment cycles were repeated every 28 days. In the case of unexpected respiratory symptoms such as dyspnea on exertion, crackles on physical examination, radiological bilateral ground-glass opacities and non-resolving pneumonia, LENALIDOMIDE should be discontinued until further investigation excludes hypersensitivity pneumonitis-like syndrome.
Table 2 summarizes the number and percentage of subjects with Grade 1-4 adverse events reported in ≥ 5% of subjects in either treatment group.
Table 2: Summary of adverse events reported in ≥ 5%
of the subjects in the Controlled Multiple Myeloma Studies
| System organ class/ Preferred term | Lenalidomide /dexamethasone (N=353) | PLACEBO /dexamethasone (N=350) |
|---|---|---|
| Subjects With At Least One Adverse Event | 353 (100.0) | 350 (100.0) |
| General Disorders And Administration Site Conditions | 303 (85.8) | 278 (79.4) |
| Fatigue | 161 (45.6) | 147 (42.0) |
| Asthenia | 103 (29.2) | 94 (26.9) |
| Pyrexia | 100 (28.3) | 83 (23.7) |
| Edema Peripheral | 95 (26.9) | 75 (21.4) |
| Edema NOS | 37 (10.5) | 33 (9.4) |
| Chest Pain | 30 (8.5) | 21 (6.0) |
| Lethargy | 26 (7.4) | 8 (2.3) |
| Pain NOS | 25 (7.1) | 27 (7.7) |
| System organ class/ Preferred term | Lenalidomide /dexamethasone (N=353) | PLACEBO /dexamethasone (N=350) |
|---|---|---|
| Gastrointestinal Disorders | 284 (80.5) | 244 (69.7) |
| Constipation | 149 (42.2) | 77 (22.0) |
| Diarrhea NOS | 137 (38.8) | 98 (28.0) |
| Nausea | 92 (26.1) | 76 (21.7) |
| Dyspepsia | 59 (16.7) | 51 (14.6) |
| Vomiting NOS | 42 (11.9) | 32 (9.1) |
| Abdominal Pain NOS | 37 (10.5) | 22 (6.3) |
| Abdominal Pain Upper | 29 (8.2) | 20 (5.7) |
| Dry Mouth | 27 (7.6) | 13 (3.7) |
| Stomatitis | 22 (6.2) | 19 (5.4) |
| Flatulence | 20 (5.7) | 16 (4.6) |
| Abdominal Distension | 15 (4.2) | 20 (5.7) |
| Musculoskeletal And Connective Tissue Disorders | 282 (79.9) | 246 (70.3) |
| Muscle Cramp | 121 (34.3) | 76 (21.7) |
| Back Pain | 91 (25.8) | 67 (19.1) |
| Arthralgia | 63 (17.8) | 63 (18.0) |
| Muscle Weakness NOS | 56 (15.9) | 56 (16.0) |
| Bone Pain | 51 (14.4) | 40 (11.4) |
| Pain In Limb | 41 (11.6) | 33 (9.4) |
| Myalgia | 37 (10.5) | 38 (10.9) |
| Chest Wall Pain | 28 (7.9) | 21 (6.0) |
| Nervous System Disorders | 275 (77.9) | 221 (63.1) |
| Headache | 94 (26.6) | 85 (24.3) |
| Dizziness | 83 (23.5) | 59 (16.9) |
| Tremor | 75 (21.2) | 26 (7.4) |
| Dysgeusia | 54 (15.3) | 34 (9.7) |
| Paraesthesia | 51 (14.4) | 47 (13.4) |
| Hypoaesthesia | 37 (10.5) | 26 (7.4) |
| Peripheral Neuropathy NOS | 31 (8.8) | 23 (6.6) |
| Neuropathy NOS | 23 (6.5) | 14 (4.0) |
| Respiratory, Thoracic And Mediastinal Disorders | 258 (73.1) | 213 (60.9) |
| Cough | 90 (25.5) | 86 (24.6) |
| Dyspnea NOS | 85 (24.1) | 60 (17.1) |
| Nasopharyngitis | 65 (18.4) | 31 (8.9) |
| Pharyngitis | 53 (15.0) | 34 (9.7) |
| Bronchitis NOS | 41 (11.6) | 30 (8.6) |
| Epistaxis | 28 (7.9) | 29 (8.3) |
| Hoarseness | 22 (6.2) | 17 (4.9) |
| Hiccups | 21 (5.9) | 17 (4.9) |
| Dyspnea Exertional | 18 (5.1) | 18 (5.1) |
| Infections And Infestations | 243 (68.8) | 200 (57.1) |
| Upper Respiratory Tract Infection NOS | 87 (24.6) | 55 (15.7) |
| Pneumonia NOS | 49 (13.9) | 30 (8.6) |
| Urinary Tract Infection NOS | 31 (8.8) | 19 (5.4) |
| Sinusitis NOS | 30 (8.5) | 17 (4.9) |
| Oral Candidiasis | 22 (6.2) | 19 (5.4) |
| Herpes Simplex | 21 (5.9) | 18 (5.1) |
| Respiratory Tract Infection NOS | 18 (5.1) | 11 (3.1) |
| Blood And Lymphatic System Disorders | 224 (63.5) | 120 (34.3) |
| Neutropenia | 152 (43.1) | 23 (6.6) |
| Anemia NOS | 119 (33.7) | 83 (23.7) |
| System organ class/ Preferred term | Lenalidomide /dexamethasone (N=353) | PLACEBO /dexamethasone (N=350) |
|---|---|---|
| Thrombocytopenia | 80 (22.7) | 37 (10.6) |
| Leukopenia NOS | 30 (8.5) | 7 (2.0) |
| Lymphopenia | 20 (5.7) | 6 (1.7) |
| Psychiatric Disorders | 209 (59.2) | 207 (59.1) |
| Insomnia | 129 (36.5) | 133 (38.0) |
| Depression | 45 (12.7) | 37 (10.6) |
| Anxiety | 35 (9.9) | 33 (9.4) |
| Confusional State | 33 (9.3) | 24 (6.9) |
| Irritability | 24 (6.8) | 16 (4.6) |
| Mood Alteration NOS | 10 (2.8) | 28 (8.0) |
| Skin And Subcutaneous Tissue Disorders | 202 (57.2) | 158 (45.1) |
| Rash NOS | 76 (21.5) | 35 (10.0) |
| Sweating Increased | 34 (9.6) | 25 (7.1) |
| Dry Skin | 33 (9.3) | 16 (4.6) |
| Pruritus | 26 (7.4) | 18 (5.1) |
| Contusion | 21 (5.9) | 17 (4.9) |
| Night Sweats | 18 (5.1) | 17 (4.9) |
| Face Edema | 15 (4.2) | 20 (5.7) |
| Metabolism And Nutrition Disorders | 188 (53.3) | 148 (42.3) |
| Anorexia | 57 (16.1) | 36 (10.3) |
| Hyperglycemia NOS | 57 (16.1) | 50 (14.3) |
| Hypokalemia | 52 (14.7) | 21 (6.0) |
| Hypocalcaemia | 34 (9.6) | 10 (2.9) |
| Hypomagnesaemia | 27 (7.6) | 10 (2.9) |
| Appetite Decreased NOS | 25 (7.1) | 14 (4.0) |
| Dehydration | 25 (7.1) | 14 (4.0) |
| Investigations | 156 (44.2) | 129 (36.9) |
| Weight Decreased | 68 (19.3) | 53 (15.1) |
| Weight Increased | 20 (5.7) | 29 (8.3) |
| Vascular Disorders | 127 (36.0) | 80 (22.9) |
| Deep Vein Thrombosis | 32 (9.1) | 15 (4.3) |
| Hypertension NOS | 30 (8.5) | 22 (6.3) |
| Hypotension NOS | 26 (7.4) | 16 (4.6) |
| Eye Disorders | 121 (34.3) | 91 (26.0) |
| Vision Blurred | 60 (17.0) | 40 (11.4) |
| Endocrine Disorders | 32 (9.1) | 22 (6.3) |
| Cushingoid | 21 (5.9) | 16 (4.6) |
System organ classes and preferred terms are coded using the MedDRA dictionary.
System organ classes and preferred terms are listed in descending order of frequency for the Overall column. A subject with multiple occurrences of an AE is counted only once in the AE category.
Table 3 summarizes the Grade 3/4 adverse events reported in ≥2% of subjects in either treatment group.
Table 3: Incidence of grade 3/4 adverse events reported in ≥2% of subjects in Either Treatment Group
| Preferred term** | Lenalidomide /dexamethasone (N=353) | PLACEBO /dexamethasone (N=350) |
|---|---|---|
| Subjects With At Least One Grade 3 / 4 AE | 294 | 244 |
| Neutropenia | 125 (35.4) | 12 (3.4) |
| Preferred term** | Lenalidomide /dexamethasone (N=353) | PLACEBO /dexamethasone (N=350) |
|---|---|---|
| Thrombocytopenia | 46 (13.0) | 22 (6.3) |
| Anemia NOS | 38 (10.8) | 21 (6.0) |
| Pneumonia NOS | 32 (9.1) | 19 (5.4) |
| Deep Vein Thrombosis | 28 (7.9) | 12 (3.4) |
| Hyperglycemia NOS | 27 (7.6) | 27 (7.7) |
| Fatigue | 23 (6.5) | 17 (4.9) |
| Hypokalemia | 20 (5.7) | 5 (1.4) |
| Muscle Weakness NOS | 20 (5.7) | 11 (3.1) |
| Asthenia | 17 (4.8) | 18 (5.1) |
| Hypocalcaemia | 16 (4.5) | 6 (1.7) |
| Atrial Fibrillation | 14 (4.0) | 4 (1.1) |
| Leukopenia NOS | 14 (4.0) | 1 (0.3) |
| Pulmonary Embolism | 14 (2.0) | 3 (0.9) |
| Diarrhea NOS | 11 (3.1) | 4 (1.1) |
| Lymphopenia | 11 (3.1) | 4 (1.1) |
| Depression | 10 (2.8) | 6 (1.7) |
| Dyspnea NOS | 10 (2.8) | 10 (2.9) |
| Hypophosphatemia | 10 (2.8) | 0 (0.0) |
| Syncope | 10 (2.8) | 4 (1.1) |
| Bone Pain | 8 (2.3) | 5 (1.4) |
| Confusional State | 8 (2.3) | 10 (2.9) |
| Constipation | 8 (2.3) | 2 (0.6) |
| Febrile Neutropenia | 8 (2.3) | 0 (0.0) |
| Dizziness | 7 (2.0) | 3 (0.9) |
| Nausea | 7 (2.0) | 2 (0.6) |
| Neuropathy NOS | 7 (2.0) | 4 (1.1) |
| Dehydration | 6 (1.7) | 8 (2.3) |
| Hypertension NOS | 6 (1.7) | 7 (2.0) |
| Pyrexia | 5 (1.4) | 12 (3.4) |
| Renal Failure NOS | 5 (1.4) | 11 (3.1) |
| Respiratory Tract Infection NOS | 4 (1.1) | 7 (2.0) |
| Hypotension NOS | 3 (0.8) | 7 (2.0) |
*Adverse events with frequency ≥ 1% in the 10 mg. Grade 3 and 4 are based on National Cancer Institute Common Toxicity Criteria version 2.
**Preferred Terms are coded using the MedDRA dictionary. A patient with multiple occurrences of an AE is counted only once in the Preferred Term category.
In 2 pivotal studies of patients with multiple myeloma who had been treated with 1 prior therapy, the following serious adverse events (considered related to study drug treatment) were reported:
The frequency of undesirable effects was calculated using the CIOMS IV working group recommendation criteria:
Very common ≥1/10 (≥10%)
Common (frequent) ≥1/100 and <1/10 (≥1% and < 10%)
Uncommon (infrequent) ≥1/1000 and <1/100 (≥0.1% and < 1%)
Rare ≥1/10,000 and <1/1000 (≥0.01% and < 0.1%)
Very rare < 1/10,000 (<0.01%)
Blood and Lymphatic system disorders:
Common: febrile neutropenia, neutropenia, anemia NOS, thrombocytopenia
Uncommon: pancytopenia, lymphadenopathy
Cardiac disorders:
Common: atrial fibrillation
Uncommon: cardiac failure congestive, atrial flutter
Endocrine disorders:
Uncommon: adrenal insufficiency NOS
Eye disorders:
Uncommon: blindness
Gastrointestinal disorders:
Uncommon: abdominal pain NOS, constipation, caecitis, diarrhea NOS, gastrointestinal hemorrhage NOS, peptic ulcer hemorrhage
General disorders and administration site conditions:
Common: pyrexia
Uncommon: general physical health deterioration, asthenia, edema peripheral
Infections and infestations:
Common: pneumonia NOS
Uncommon: cellulitis, sepsis NOS, bronchopneumonia NOS, herpes zoster ophthalmic, Pneumocystis carnii pneumonia, septic shock, urinary tract infection NOS, bursitis infective NOS, Clostridium difficile sepsis, Enterobacter bacteremia, Escherichia sepsis, herpes zoster, lobar pneumonia NOS, meningitis, neutropenic sepsis, pneumonia bacterial NOS, pneumonia pneumoccal, pneumonia primary atypical, respiratory tract infection NOS, sinusitis NOS, subacute endocarditis, upper respiratory tract infection NOS
Investigations:
Uncommon: international normalized ratio increased, blood creatinine increased, hemoglobin decreased, weight decreased, white blood cell count decreased
Metabolism and nutrition disorders:
Common: hyperglycemia NOS
Uncommon: dehydration, hypocalcaemia, hypokalemia
Musculoskeletal and connective tissue disorders:
Uncommon: muscle weakness NOS, myopathy steroid, back pain, spondylitis NOS
Neoplasms benign, malignant and unspecified (incl. cysts and polyps):
Uncommon: basal cell carcinoma, squamous cell carcinoma, glioblastoma multiforme, fibrous histiocytoma, breast carcinoma in situ, bronchoalveolar carcinoma, lung adenocarcinoma, prostate cancer, and transitional cell carcinoma*
* Each solid tumor listed as “Uncommon” above occurred in 1/353 patients.
Nervous system disorders:
Common: cerebrovascular accident
Uncommon: cerebral ischemia, dizziness, leukoencephalopathy, memory impairment, intracranial hemorrhage NOS, intracranial venous sinus thrombosis NOS, polyneuropathy NOS, somnolence
Psychiatric disorders:
Uncommon: depression, confusional state, delusion NOS, insomnia
Renal and urinary disorders:
Uncommon: renal failure NOS, renal failure acute, Fanconi syndrome acquired, hematuria, renal tubular necrosis, urinary retention
Respiratory, thoracic and mediastinal disorders:
Common: pulmonary embolism
Skin and subcutaneous tissue disorders:
Uncommon: skin discoloration
Vascular disorders:
Uncommon: venous thrombosis NOS limb, phlebitis NOS, hypotension NOS, peripheral ischemia, circulatory collapse, hypertension NOS, orthostatic hypotension, phlebitis superficial
Post-Market Adverse Drug Reactions
The following adverse drug reactions have been identified from the worldwide post-marketing experience with lenalidomide. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure:
Allergic reactions: angioedema, anaphylaxis, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug
reaction with eosinophilia and systemic symptoms
Endocrine Disorders: hyperthyroidism, hypothyroidism
Gastrointestinal Disorders: pancreatitis
General Disorders and Administrative Site Conditions: drug ineffective, drug intolerance, swelling, chills, edema, gait disturbance, feeling abnormal
Hepatobiliary Disorders: hepatic failure, acute hepatic failure, toxic hepatitis, cytolytic hepatitis, hepato-renal failure, cholestasis, cholestatic hepatitis, and mixed cytolytic/cholestatic hepatitis
Immune System Disorders: acute graft versus host disease, solid organ transplant rejection
Infections and Infestations: Viral reactivation including herpes zoster virus, hepatitis B virus, progressive multifocal leukoencephalopathy
Injury, Poisoning and Procedural Complications: hip fracture, fall
Investigations: RBC count decreased, platelet count decreased, WBC count decreased, blood pressure decreased, full blood count abnormal, hematocrit decreased, transient abnormal liver laboratory tests (predominantly transaminases). Treatment should be interrupted and restarted at a lower dose once levels return to baseline. Successful re-challenge without recurrence of liver laboratory elevation was reported in some patients.
Metabolism and Nutrition Disorders: tumor lysis syndrome (TLS) and tumor flare reaction (TFR)
Musculoskeletal Disorders: pain in extremity, rhabdomyolysis
Neoplasms benign, malignant and unspecified: multiple myeloma, leukemia, acute leukemia, acute myeloid leukemia, neoplasm progression, myelodysplastic syndromes
Nervous System Disorders: balance disorder, hypoesthesia
Renal Disorders: renal impairment
Reproductive System and Breast Disorders: breast mass, breast pain, erectile dysfunction
Respiratory, Thoracic and Mediastinal Disorders: dyspnea, interstitial pneumonitis, dysphonia, cough
Skin and Subcutaneous Tissue Disorders: pruritus, rash maculo-papular, skin exfoliation, erythema, swelling face, hyperhidrosis, urticaria, rash generalized.
DRUG INTERACTIONS
Overview
In vitro lenalidomide is not a substrate, inhibitor or inducer of cytochrome P450 enzymes. Hence co-administration of cytochrome P450 substrates or inhibitors with lenalidomide is not likely to result in clinically relevant drug-drug interactions.
Drug-Drug Interactions
Table 4: Established or Potential Drug-Drug Interactions
| Proper name | Ref | Effect | Clinical comment |
| digoxin | CT | When co-administered with lenalidomide, the digoxin AUC was not significantly different, however, the digoxin Cmax was increased by 14%. | Periodic monitoring of digoxin plasma levels, in accordance with clinical judgment and based on standard clinical practice in patients receiving this medication, is recommended during administration of LENALIDOMIDE. |
| warfarin | CT | Co-administration of multiple doses of 10 mg of lenalidomide had no effect on the single dose pharmacokinetics of R- and S- warfarin. Co-administration of single 25-mg dose of warfarin had no effect on the pharmacokinetics of total lenalidomide. | Expected changes in laboratory assessments of PT and INR were observed after warfarin administration, but these changes were not affected by concomitant lenalidomide administration. Periodic monitoring of warfarin plasma levels, in accordance with clinical judgment and based on standard clinical practice in patients receiving this medication, is recommended during administration of LENALIDOMIDE. |
Legend: CT = Clinical Trial; INR = International Normalized Ratio; PT = Prothrombin Time
The risk of DVT and PE may potentially be increased with the simultaneous use of erythropoietic agents or Hormone Replacement Therapy in menopause.
Hormonal contraceptives are not recommended due to the increased risk of venous thromboembolic disease.
Drug-Food Interactions
LENALIDOMIDE is absorbed equally well with or without food.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
LENALIDOMIDE may be associated with dizziness and fatigue. Therefore, patients are advised to be cautious when operating machinery, or when driving.
DOSAGE AND ADMINISTRATION
Dosing Considerations
LENALIDOMIDE capsules should be taken orally at about the same time each day. The capsules should not be broken, chewed, opened or handled extensively. The capsules should be swallowed whole, preferably with water, either with or without food.
Recommended Dose and Dosage Adjustment
- Multiple Myeloma
Recommended Starting Dose
The recommended starting dose of LENALIDOMIDE for multiple myeloma patients is 25 mg/day administered as a single 25 mg capsule on Days 1-21 of repeated 28-day cycles in combination with dexamethasone.
In the treatment of transplant non-eligible newly diagnosed multiple myeloma (TNE NDMM) the recommended dose of dexamethasone is 40 mg orally once weekly (in patients > 75 years of age, the dexamethasone dose should be reduced to 20 mg once weekly) on days 1, 8, 15, and 22 of repeated 28-day cycles.
For previously treated multiple myeloma patients, refer to Clinical Trials for the dosing specifics of dexamethasone. Consideration should be given to the dose of dexamethasone used in combination with LENALIDOMIDE in previously treated multiple myeloma patients (see WARNINGS AND PRECAUTIONS, General). In a Phase 3 clinical trial in newly diagnosed MM patients including both those that were transplant non-eligible and transplant eligible (newly diagnosed transplant-eligible is an unauthorized indication), patients randomized to the lenalidomide /standard dose dexamethasone arm received lenalidomide 25 mg/day, Days 1-21 every 28 days plus dexamethasone 40 mg/day on Days 1-4, 9-12, and 17-20 of each 28-day cycle for the first 4 cycles of therapy and then 40 mg/day orally on Days 1-4 every 28 days. Patients randomized to the lenalidomide /low dose dexamethasone arm received lenalidomide 25 mg/day, Days 1-21 every 28 days plus low dose dexamethasone 40 mg/day once weekly on Days 1, 8, 15, and 22 every 28 days.
Dosing of LENALIDOMIDE in combination with dexamethasone is continued or modified based upon clinical and laboratory findings until disease progression or intolerance.
Patients on therapy for Multiple Myeloma should have their complete blood counts monitored every 7 days (weekly) for the first 2 cycles (8 weeks), on days 1 and 15 of cycle 3, and every 28 days (4 weeks) thereafter. Patients may require dose interruption and/or reduction.
Recommended Starting Dose Adjustment for Renal Impairment:
Since lenalidomide is primarily excreted unchanged by the kidney, starting dose adjustment is recommended in patients with renal insufficiency in order to maintain an effective and safe level of LENALIDOMIDE. No dose adjustments are required for patients with CrCL ≥ 60 mL/min. A LENALIDOMIDE starting dose adjustment should be considered for patients with CrCL < 60 mL/min.
The recommendations for initial starting doses of LENALIDOMIDE for patients with MM are as follows while maintaining a 21 out of 28 day treatment cycle:
| Renal Function (CrCL) | Multiple Myeloma Dose |
Mild Renal Impairment (90 > CrCL ≥ 60 mL/min) | 25 mg (Normal Dose) Every 24 hours |
| Moderate Renal Impairment | 10 mga |
| (30 ≤ CrCL < 60 mL/min) | Every 24 hours |
Severe Renal Impairment (CrCL < 30 mL/min, not requiring dialysis) | 15 mg Every 48 hours |
End Stage Renal Disease (CrCL < 30 mL/min, requiring dialysis) | 5 mg Once daily. On dialysis days the dose should be administered following dialysis |
a. The dose may be escalated to 15 mg every 24 hours after 2 cycles if patient is not responding to treatment and is tolerating the drug.
After initiation of LENALIDOMIDE therapy, subsequent LENALIDOMIDE dose modification should be based on individual patient treatment tolerance, as described below.
Recommended Dosage Adjustment
Dose modification guidelines, as summarized below are recommended to manage Grade 3 or 4 neutropenia or thrombocytopenia or other Grade 3 or 4 toxicity judged to be related to LENALIDOMIDE.
Platelet counts
Thrombocytopenia
| Newly Diagnosed Multiple Myeloma | |
| When Platelets | Recommended Course |
| Fall to < 25,000/mcL | Interrupt LENALIDOMIDE treatment, follow CBC weekly |
| Return to ≥ 50,000/mcL | Restart LENALIDOMIDE at 5 mg less than the previous dose. If previous dose was 5 mg, restart LENALIDOMIDE at 2.5 mg. Do not dose below 2.5 mg daily. |
| Previously Treated Multiple Myeloma | |
| When Platelets | Recommended Course |
| Fall to <30,000/mcL | Interrupt LENALIDOMIDE treatment, follow CBC weekly |
| Return to ≥30,000/mcL | Restart LENALIDOMIDE at 15 mg daily (if starting dose was 25 mg daily), or 5 mg less than the adjusted starting dose. |
| For each subsequent drop <30,000/mcL | Interrupt LENALIDOMIDE treatment |
| Return to ≥30,000/mcL | Resume LENALIDOMIDE at 5 mg less than the previous dose. Do not dose below 5 mg daily |
Neutrophil counts (ANC)
Neutropenia
| Newly Diagnosed Multiple Myeloma | |
| When ANC | Recommended Course |
Fall to < 500/mcL or febrile neutropenia (ANC < 1000/mcL & fever ≥ 38.5◦ C) | Interrupt LENALIDOMIDE treatment, add G-CSF, follow CBC weekly |
| Return to ≥ 1,000/mcL and neutropenia is the only toxicity | Resume LENALIDOMIDE at starting dose |
| Return to ≥ 1,000/mcL and if other toxicity | Restart LENALIDOMIDE at 5 mg less than the previous dose. If previous dose was 5 mg, restart LENALIDOMIDE at 2.5 mg. Do not dose below 2.5 mg daily. |
| For each subsequent drop < 500/mcL or febrile neutropenia (ANC <1000/mcL &fever ≥ 38.5◦ C) | Interrupt LENALIDOMIDE treatment |
| Return to ≥1,000/mcL | Resume LENALIDOMIDE at 5 mg less than the previous dose. If previous dose was 5 mg, restart LENALIDOMIDE at 2.5 mg. Do not dose below 2.5 mg daily. |
| Previously Treated Multiple Myeloma | |
| When ANC | Recommended Course |
| Fall to <1000/mcL | Interrupt LENALIDOMIDE treatment, add G-CSF, follow CBC weekly |
| Return to ≥1,000/mcL and neutropenia is the only toxicity | Resume LENALIDOMIDE at 25 mg daily (or adjusted starting dose). |
| Return to ≥1,000/mcL and if other toxicity | Resume LENALIDOMIDE at 15 mg daily (if starting dose was 25 mg daily), or 5 mg less than the adjusted starting dose. |
| For each subsequent drop <1,000/mcL | Interrupt LENALIDOMIDE treatment |
| Return to ≥1,000/mcL | Resume LENALIDOMIDE at 5 mg less than the previous dose. Do not dose below 5 mg daily |
ANC = Absolute neutrophil count; CBC = complete blood count; GCSF= granulocyte colony stimulating factor
Other Grade 3/4 Toxicities
For other Grade 3/4 toxicities judged to be related to LENALIDOMIDE, hold treatment and restart at a lower dose level when toxicity has resolved to ≤ Grade 2.
LENALIDOMIDE interruption or discontinuation should be considered for Grade 2-3 skin rash.
LENALIDOMIDE must be discontinued for angioedema, skin rash Grade 4, exfoliative or bullous rash, or if SJS, TEN or DRESS is suspected, and should not be resumed following discontinuation from these reactions (see WARNINGS AND PRECAUTIONS, Immune).
Missed Dose
If less than 12 hours has elapsed since missing a dose, the patient can take the dose. If more than 12 hours has elapsed since missing a dose at the normal time, the patient should not take the dose, but take the next dose at the normal time on the following day. Patients should not take 2 doses at the same time.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
Information on overdosage of lenalidomide is limited. No cases of overdose have been reported during the clinical studies. The highest single dose of lenalidomide that has been ingested in humans in healthy volunteers is 400 mg and the highest multiple dose is 200 mg/day, administered as 100 mg twice daily for six days. There is no known specific antidote for lenalidomide overdosage and treatment must be symptomatic. In the event of an overdosage, frequent monitoring of the patient’s vital signs and blood counts over the following 2 weeks along with close patient monitoring are indicated. Appropriate supportive care should be administered.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The mechanism of action of lenalidomide remains to be fully characterized; however, multiple mechanisms of action have been identified that affect cancer cells and their microenvironment.
Lenalidomide increases hemoglobin expression by erythroid cells; inhibits proliferation of certain hematopoietic tumor cells (including tumor cells with or without deletions of chromosome 5 and MM tumor cells); enhances T cell and Natural Killer cell number and activity; inhibits angiogenesis by blocking the migration and adhesion of endothelial cells and the formation of microvessels; and inhibits production of pro-inflammatory cytokines (e.g., TNF-α and IL-6) by monocytes.
Pharmacodynamics
In healthy volunteers, multiple dosing with lenalidomide appeared to have an effect upon the immune response. The highest dose was 200 mg/day. Dosing occurred once on the morning of Days 1 and 8 and twice daily on Days 2 to 7 inclusive. Statistically significant dose-related decrease in both CD4 and CD8 blood counts was observed from Day 4 onwards. For CD4 counts, the magnitude of the decreases was relatively constant (approximately 300/mm3) on Days 4, 6 and 8, with values approaching 433/mm3. The decrease in mean CD8 counts were up to 242/mm3 on Day 8, with levels still considerably lower than the baseline value at the post-study assessment.
Electrocardiography
A double-blind, randomised, placebo- and active-controlled, single-dose, four-period crossover study was performed to investigate the effects of lenalidomide 10 mg and 50 mg on ECG parameters in healthy male subjects (N=52). Lenalidomide at 10 mg and 50 mg single doses was not observed to affect the QTcF interval, the QRS duration, the PR interval, or heart rate in a treatment related manner.
- Multiple Myeloma
Treatment with lenalidomide in MM patients is associated with the induction of antiproliferative effects and apoptosis in malignant myeloma cells due to direct antitumor activity, the alteration of the bone marrow microenvironment, and immune modulation.
Pharmacokinetics
The pharmacokinetics of lenalidomide were evaluated in a single-blind, placebo-controlled, ascending single oral-dose study (see Table 5). Single oral doses of 5, 20, 50, 100, 200 and 400 mg were administered in the fasted state. Nineteen subjects entered the study and 15 completed the study.
Table 5: Summary of Pharmacokinetic Parameters in a healthy male volunteers
Geometric Mean
| Dose | Cmax (ng/mL) | T1/2 (h) | AUC(0-∞) (ng∙h/mL) | Apparent Oral Clearance (mL/min) | Apparent Volume of distribution (L) |
|---|---|---|---|---|---|
| 5 mg | 66.2 | 3.24 | 276 | 302 | 84.6 |
| 20 mg | 373 | 3.66 | 1391 | 240 | 76.0 |
| 50 mg | 808 | 3.46 | 2546 | 327 | 98.1 |
| 100 mg | 1735 | 4.71 | 5997 | 278 | 113 |
| 200 mg | 3519 | 5.16 | 12111 | 275 | 123 |
| 400 mg | 4586 | 8.72 | 21895 | 304 | 230 |
No formal bioavailability studies were performed in humans.
Absorption:
Lenalidomide, in healthy volunteers, is rapidly absorbed following oral administration with maximum plasma concentrations occurring between 0.625 and 1.5 hours post-dose. Co-administration with food does not alter the extent of absorption (AUC) but does reduce the maximal plasma concentration (Cmax) by 36%. The pharmacokinetic disposition of lenalidomide is linear. Cmax and AUC increase proportionately with increases in dose. Multiple dosing at the recommended dose-regimen does not result in drug accumulation.
In MM patients maximum plasma concentrations occurred between 0.5 and 4.0 hours post-dose both on Days 1 and 28. AUC and Cmax values increase proportionally with dose following single and multiple doses. Exposure (AUC) in multiple myeloma patients was 57% higher than in healthy male volunteers.
Distribution:
In vitro (14C)-lenalidomide binding to plasma proteins is approximately 23-29%.
Lenalidomide is present in semen (<0.01% of the dose) after the administration of 25 mg/day. Lenalidomide is undetectable in the semen of healthy volunteers three days after discontinuation of the drug.
Metabolism:
Lenalidomide is not a substrate of hepatic metabolic enzymes in vitro. Unchanged lenalidomide is the predominant circulating component in vivo in humans. Two identified metabolites are hydroxy-lenalidomide and N-acetyl-lenalidomide; each constitutes less than 5% of parent levels in circulation.
In vitro in human liver preparations lenalidomide does not undergo oxidative (cytochrome P450) or conjugative metabolism. Non-enzymatic hydrolysis of lenalidomide occurs in aqueous media and plasma. In vitro lenalidomide does not inhibit or induce cytochrome P450 enzymes, suggesting that clinically relevant drug-drug interactions with cytochrome P450 substrates are unlikely.
Excretion:
In healthy volunteers, approximately two-thirds of lenalidomide is eliminated unchanged through urinary excretion. The process exceeds the glomerular filtration rate and therefore active secretion may have some contribution in the overall renal excretion of lenalidomide. Lenalidomide is a weak substrate, but not an inhibitor of P-glycoprotein, suggesting that drug-drug interactions are unlikely with P-glycoprotein substrates and inhibitors.
At recommended doses (5 to 25 mg/day), half-life in plasma is approximately 3 hours in healthy volunteers and ranged from 3 to 5 hours in patients with multiple myeloma.
Special Populations and Conditions
Pediatrics: No pharmacokinetic (PK) data are available in patients below the age of 18 years.
Geriatrics: No dedicated clinical studies have been conducted to evaluate pharmacokinetics of lenalidomide in the elderly. Population PK analyses included patients with ages ranging from 39 to 85 years old, of which 40.8 % were older than 65 years of age, and show that age does not influence the disposition of lenalidomide.
Gender: Based on a population PK analysis of pooled PK dataset containing 147 patients (M/F, 102/45) gender has no effect on lenalidomide pharmacokinetics.
Race: Based on PK studies in Asian patients, there are no clinically relevant differences in the lenalidomide PK parameters when compared to PK parameters obtained in Caucasian patients [see DETAILED PHARMACOLOGY].
Hepatic Insufficiency: Population PK analyses included patients with mild hepatic impairment (N = 16, total bilirubin >1.0 to ≤ 1.5 x ULN or AST > ULN) and show that mild hepatic impairment does not influence the disposition of lenalidomide. There are no data available for patients with moderate to severe hepatic impairment.
Renal Insufficiency: The pharmacokinetics of lenalidomide were studied in patients with renal impairment due to nonmalignant conditions. In this study, 5 patients with mild renal function impairment (CrCL 56-74 mL/min), 6 patients with moderate renal function impairment (CrCL 33-46 mL/min), 6 patients with severe renal function impairment (CrCL 17-29 mL/min), and 6 patients with end stage renal disease requiring dialysis were administered a single oral 25 mg dose of lenalidomide. As a control group comparator, 7 healthy subjects of similar age with normal renal function (CrCL 83-145 mL/min) were also administered a single oral 25 mg dose of lenalidomide. The pharmacokinetic parameters of lenalidomide were similar in patients with mild impairment and healthy subjects. Patients with moderate and severe renal impairment had a 3-fold increase in half-life and up to 75% decrease in clearance compared to healthy subjects. Patients with end stage renal disease on hemodialysis had an approximately 4.5-fold increase in half-life and an 80% decrease in clearance compared to healthy subjects. Approximately 30% of the drug in the body was removed by a 4-hour dialysis session.
Mean AUC∞ was increased by 137%, 274% and 372% in patients with moderate, severe and end stage renal disease, respectively, as compared to that of normal and mild groups combined (n=12). Renal impairment had no effect on oral absorption (Cmax and tmax).
STORAGE AND STABILITY
Store at 15-30ºC.
SPECIAL HANDLING INSTRUCTIONS
Currently, no published data are available regarding the cutaneous absorption of lenalidomide. Most health care institutions recommend that latex gloves be worn while handling chemotherapeutic agents. Health care providers may consider wearing gloves when directly handling LENALIDOMIDE capsules, along with standard hand washing. Females who could become pregnant, or who plan to become pregnant can handle LENALIDOMIDE capsules if they are using latex gloves.
Patients should be instructed to not extensively handle or open the capsules and to maintain storage of capsules in blister packs until ingestion wherever possible. If there is contact with non-intact LENALIDOMIDE capsules or the powder contents, the exposed area should be washed with soap and water.
Repackaging of LENALIDOMIDE must only be done on exceptional circumstances. This should only be done by pharmacists.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each capsule contains the active ingredient, lenalidomide.
Each capsule contains the nonmedicinal ingredient: lactose anhydrous. The additional composition of the different capsule strengths is provided in the table below.
| Strength | Imprint* | Composition | Package Size | |
| 2.5 mg | NAT, 2.5 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters |
| 5 mg | NAT, 5 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters 28’s (4x7s) Blisters |
| 7.5 mg | NAT, 7.5 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters |
| 10 mg | NAT, 10 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters 28’s (4x7s) Blisters |
| 15 mg | NAT, 15 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters |
| 20 mg | NAT, 20 mg | Gelatin, titanium dioxide, FD & C blue # 1, yellow iron oxide, FD & C yellow # 6 | Green/blue | 21’s (3x7s) Blisters |
| 25 mg | NAT, 25 mg | Gelatin, titanium dioxide | White/white | 21’s (3x7s) Blisters |
*Imprint is in black ink
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: lenalidomide
Chemical name: 3-(4-amino-1-oxo 1,3-dihydro-2H-isoindol-2-yl) piperidine-2,6-dione
Molecular formula and molecular mass: C13H13N3O3, 259.3 g/mol
Structural formula:
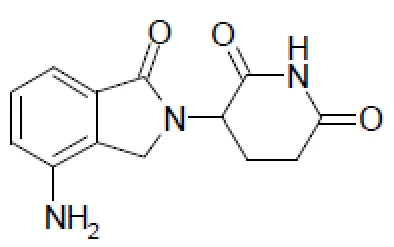
Physicochemical properties: Lenalidomide is cream to light yellow powder. It is soluble in dimethylformamide, dimethylsulfoxide; slightly soluble in methanol, acetonitrile, acetone and tetrahydrofuran; practically insoluble in water. Lenalidomide has an asymmetric carbon atom and can exist as the optically active forms S(-) and R(+), and is produced as a racemic mixture with a net optical rotation of zero.
CLINICAL TRIALS
Comparative Bioavailability Study
A blinded, balanced, randomized, two-treatment, two-period, two sequence, single dose, crossover, oral comparative bioavailability study of LENALIDOMIDE capsules, 25 mg (Natco Pharma (Canada) Inc.) and REVLIMID® (lenalidomide) capsules, 25 mg (Celgene Inc.) was conducted in 33 healthy, adult, human, male subjects under fasting conditions. The results are presented below:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Lenalidomide (1 x 25 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (hr*ng/mL) | 2024.5 2052.8 (17.0) | 1987.8 2014.9 (16.4) | 102.1 | 100.4 - 103.8 |
Lenalidomide (1 x 25 mg) Geometric Mean Arithmetic Mean (CV %) |
|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
|---|---|---|---|---|
| AUCI (hr*ng/mL) | 2044.2 2072.8 (17.0) | 2006.7 2034.2 (16.4) | 102.1 | 100.4 - 103.8 |
Cmax (ng/mL) | 567.1 580.7 (22.0) | 528.7 547.3 (26.4) | 107.6 | 100.4 - 115.4 |
Tmax§ (h) | 0.70 (0.50 - 1.75) | 0.83 (0.50 - 2.00) | ||
T½€ (h) | 3.75 (17.26) | 3.78 (18.17) |
* LENALIDOMIDE capsules, 25 mg (Natco Pharma (Canada) Inc.)
† Revlimid® (lenalidomide) capsules, 25 mg (Celgene Inc., Canada)
§ Expressed as the median (range)
€ Expressed as the arithmetic mean (CV%) only
Multiple Myeloma
Phase 3 Randomized Open-Label Study in Transplant Non-Eligible Newly Diagnosed Multiple Myeloma
Study Demographics and Trial Design
A randomized, multicentre, open-label, 3-arm study [Study MM-020 (FIRST)] was conducted to evaluate the efficacy and safety of lenalidomide and low-dose dexamethasone (Rd) given for 2 different durations of time [i.e., until disease progression (Arm Rd) or for up to eighteen 28-day cycles (Arm Rd18)], to that of melphalan, prednisone, and thalidomide (Arm MPT) for a maximum of twelve 42-day cycles (72 weeks) in the treatment of newly diagnosed multiple myeloma patients who were not eligible for stem cell transplant (SCT). Key eligibility criteria included patients with newly diagnosed, previously untreated, symptomatic multiple myeloma based on International Myeloma Working Group (IMWG) 2003 criteria. Patients were 65 years of age or older, or were younger but not candidates for SCT because they declined to undergo SCT or SCT was not available to the patient due to cost or other reasons, and had an ECOG performance status of 0-2. Patients were stratified at randomization by age (≤ 75 versus > 75), stage (ISS Stages I and II versus Stage III), and country.
Patients in Arm Rd and Arm Rd18 received lenalidomide 25 mg once daily on days 1-21 of 28-day cycles. Dexamethasone was dosed 40 mg orally once weekly (in patients > 75 years of age, the dexamethasone dose was reduced to 20 mg once weekly) on days 1, 8, 15 and 22 of each 28-day cycle. Initial dose and regimens for Rd and Rd18 were adjusted according to age and renal function. All patients received prophylactic anticoagulation with the most commonly used being aspirin.
A total of 1623 patients were enrolled in the study. The baseline patient and disease-related characteristics of the patients were balanced among the 3 arms (see Table 6).
The primary efficacy endpoint, progression-free survival (PFS), was defined as the time from randomization to the first documentation of disease progression as determined by an Independent Response Adjudication Committee (IRAC) based on IMWG criteria or death from any cause. The primary comparison was between Arm Rd and Arm MPT.
Table 6: Baseline Demographic and Disease-Related Characteristics (ITT Population)
Arm Rd (N=535) | Arm Rd18 (N=541) | Arm MPT (N=547) | |
|---|---|---|---|
| Patient Characteristic | |||
Age (years) Median Min, Max Age Distributiona n (%) ≤ 75 n (%) > 75 n (%) | 73 44, 91 349 (65.2) 186 (34.8) | 73 40, 89 348 (64.3) 193 (35.7) | 73 51, 92 359 (65.6) 188 (34.4) |
Sex n (%) Male Female | 294 (55.0) 241 (45.0) | 273 (50.5) 268 (49.5) | 287 (52.5) 260 (47.5) |
Race / Ethnicity n (%) White Other | 474 (88.6) 61 (11.4) | 480 (88.7) 61 (11.3) | 491 (89.8) 56 (10.2) |
| Disease Characteristic | |||
ISS Stageb I or II III | 319 (59.6) 216 (40.4) | 322 (59.5) 219 (40.5) | 323 (59.0) 224 (41.0) |
Creatinine Clearancea < 30 mL/min ≥ 30 to 50 mL/min ≥ 50 to 80 mL/min ≥ 80 mL/min | 45 (8.4) 126 (23.6) 241 (45.0) 123 (23.0) | 47 (8.7) 120 (22.2) 252 (46.6) 122 (22.6) | 55 (10.1) 126 (23.0) 222 (40.6) 144 (26.3) |
ECOG Performance Status Grade 0 Grade 1 Grade 2 Grade ≥ 3 Missing | 155 (29.0) 257 (48.0) 119 (22.2) 2 (0.4) 2 (0.4) | 163 (30.1) 263 (48.6) 113 (20.9) 2 (0.4) 0 (0.0) | 156 (28.5) 275 (50.3) 111 (20.3) 2 (0.4) 3 (0.5) |
Cytogenetic Riskb Adverse risk Non-Adverse Risk Favourable hyperdiploidy Normal Uncertain Risk Not Evaluable Missing | 170 (31.8) 298 (55.7) 112 (20.9) 148 (27.7) 38 (7.1) 34 (6.4) 33 (6.2) | 185 (34.2) 290 (53.6) 103 (19.0) 131 (24.2) 56 (10.4) 35 (6.5) 31 (5.7) | 189 (34.6) 283 (51.7) 102 (18.6) 141 (25.8) 40 (7.3) 44 (8.0) 31 (5.7) |
Β2-microglobulin > 5.5 mg/L ≤ 5.5 mg/L Missing | 224 (41.9) 309 (57.8) 2 (0.4) | 224 (41.4) 316 (58.4) 1 (0.2) | 234 (42.8) 312 (57.0) 1 (0.2) |
a Subjects were stratified at randomization by: age, ISS stage, and renal status
b Cytogenetic risk categories are mutually exclusive. Definitions: Adverse Risk category: t(4;14), t(14;16), del(13q) or monosomy 13, del(17p), 1q gain; Non-adverse Risk categories include favourable hyperdiploidy: t(11;14), gains of 5/9/15; normal: a normal result, gains other than 5/9/15, IgH deletion; and uncertain risk: probes used for analysis cannot place subject in any of the other risk categories. Not evaluable: no specimen received, test failure, or insufficient number of cells available for analysis.
Study Results
The final analysis of PFS, the primary endpoint with 24 May 2013 data cutoff, was conducted on 960 events (59% of the ITT population). The PFS was significantly longer in Arm Rd than in Arm MPT: HR 0.72 (95% CI: 0.61, 0.85 p <0.0001) (see table 7 and Figure 1).
For the interim OS analysis with 03 March 2014 data cutoff, the median follow-up time for all surviving patients is 45.5 months with 697 death events, representing 78% of prespecified events required for the planned final OS analysis (697/896 of the final OS events). The observed OS HR was 0.75 for Arm Rd versus Arm MPT (95% CI: 0.62, 0.90) (see Table 7).
Table 7: Summary of Efficacy Results (ITT Population)
| Trial Parameter | Arm Rd (N=535) | Arm Rd18 (N=541) | Arm MPT (N=547) | |||||||
|---|---|---|---|---|---|---|---|---|---|---|
| PFS – IRAC (months)f | ||||||||||
| Number of PFS events, n(%) | 278 (52.0) | 348 (64.3) | 334 (61.1) | |||||||
| Mediana PFS time, months (95% CI)b | 25.5 (20.7, 29.4) | 20.7 (19.4, 22.0) | 21.2 (19.3, 23.2) | |||||||
HR (95% CI)c; p-valued Rd vs. MPT Rd vs. Rd18 Rd18 vs. MPT | 0.72 (0.61, 0.85); < 0.0001 0.70 (0.60, 0.82); < 0.0001 1.03 (0.89, 1.20); 0.7035 | |||||||||
| Overall Survival – Interim (months)g | ||||||||||
| Number of death events | 208 (38.9) | 228 (42.1) | 261 (47.7) | |||||||
| Mediana OS time, months (95% CI)b | 58.9 (56.0, NE) | 56.7 (50.1, NE) | 48.5 (44.2, 52.0) | |||||||
HR (95% CI)c Rd vs. MPT Rd vs. Rd18 Rd18 vs. MPT | 0.75 (0.62, 0.90) 0.91 (0.75, 1.09) 0.83 (0.69, 0.99) | |||||||||
| Myeloma Response Ratee – IRAC, n (% )f | ||||||||||
| CR | 81 (15.1) | 77 (14.2) | 51 (9.3) | |||||||
| VGPR | 152 (28.4) | 154 (28.5) | 102 (18.8) | |||||||
| PR | 169 (31.6) | 166 (30.7) | 187 (34.2) | |||||||
| Overall response: CR, VGPR, or PR | 402 (75.1) | 397 (73.4) | 341 (62.3) | |||||||
| Duration of Response-IRAC (months)f | ||||||||||
| Mediana DOR (95% CI)b | 35.0 (27.9, 43.4) | 22.1 (20.3, 24.0) | 22.3 (20.2, 24.9) | |||||||
CI = confidence interval; CR = complete response; d = low-dose dexamethasone; HR = hazard ratio; IRAC = Independent Response Adjudication Committee; M = melphalan; NE = not evaluable; OS = overall survival; P = prednisone; PFS = progression free survival; PR = partial response; R = Lenalidomide; Rd = Rd given until documentation of progressive disease; Rd18 = Rd given for ≤ 18 cycles; T = Thalidomide; VGPR = very good partial response; vs = versus.
a The median is based on the Kaplan-Meier estimate
b The 95% CI about the median
c Based on Cox proportional hazards model comparing the hazard functions associated with the indicated treatment arms d The p-value is based on the unstratified log-rank test of Kaplan-Meier curve differences between the indicated arms e Best assessment of response during the treatment phase of the study
f Data cutoff date = 24 May 2013
g Data cutoff date = 3 March 2014
Figure 1: Kaplan-Meier Curves of Progression-free Survival from Study MM -020a Between Arm Rd, Arm Rd18 and Arm MPT (ITT Population)
Cutoff date: 24 May 2013
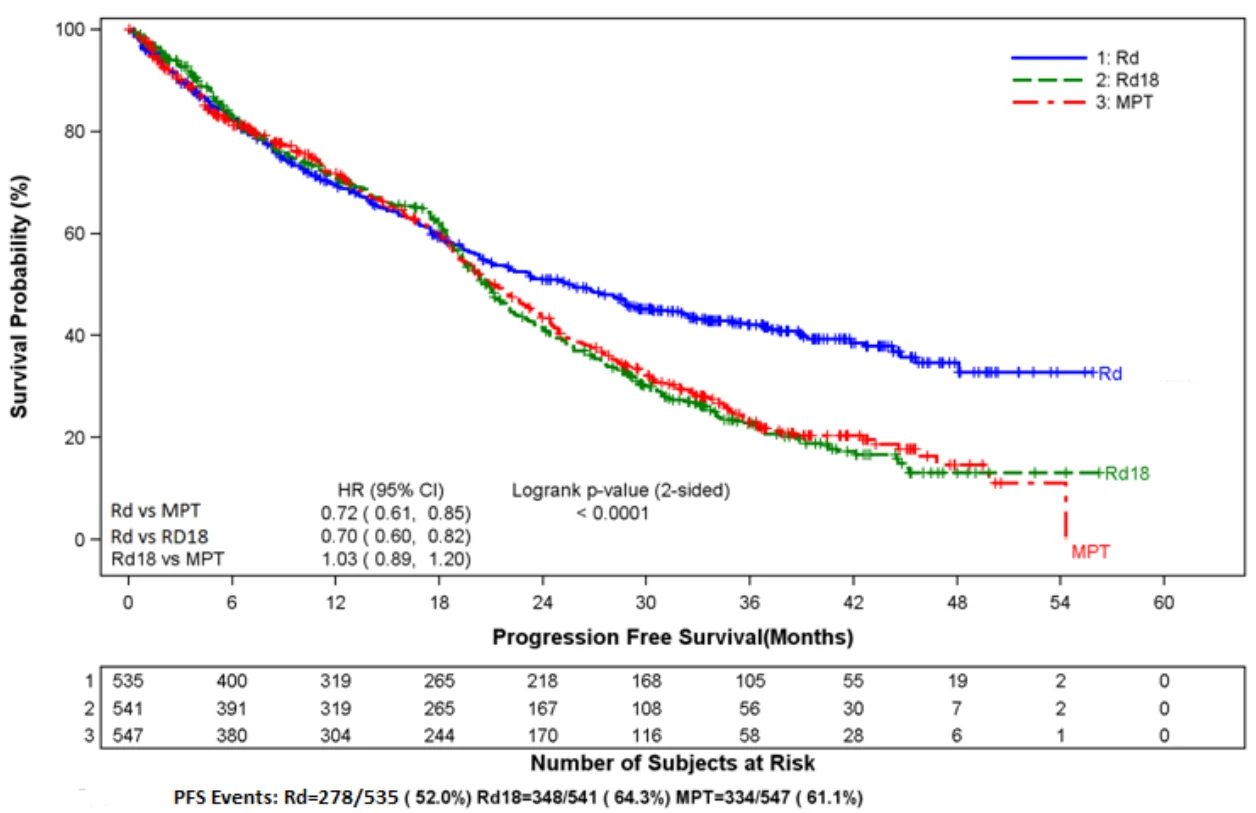
CI = confidence interval; d = low-dose dexamethasone; HR = hazard ratio; IRAC = Independent Response Adjudication Committee; M = melphalan; P = prednisone; PFS = progression free survival; R =Lenalidomide; Rd = Rd given until documentation of progressive disease; Rd18 = Rd given for ≤ 18 cycles; T = Thalidomide
a Based on IRAC Assessment
Phase 3 Randomized Double Blind Placebo-Controlled Studies in Previously Treated Multiple Myeloma Patients
Two randomized studies (Study MM-009 and MM-010) were conducted to evaluate the efficacy and safety of lenalidomide in multiple myeloma subjects who had received at least one prior therapy. These multi-center, multi-national, double-blind, placebo-controlled studies compared lenalidomide plus oral pulse high-dose dexamethasone therapy (lenalidomide/dexamethasone) to dexamethasone therapy alone (placebo/dexamethasone), in subjects with MM who had received at least one prior treatment.
In both studies, subjects in the (lenalidomide/dexamethasone) group took 25 mg of lenalidomide orally once daily on Days 1 to 21 and a matching placebo capsule once daily on Days 22 to 28 of each 28-day cycle. Subjects in the placebo/ dexamethasone group took 1 placebo capsule on Days 1 to 28 of each 28-day cycle. Subjects in both treatment groups took 40 mg of dexamethasone orally once daily on Days 1 to 4, 9 to 12, and 17 to 20 of each 28-day cycle for the first 4 cycles of therapy. The dose of dexamethasone was reduced to 40 mg orally once daily on Days 1 to 4 of each 28-day cycle after the first 4 cycles of therapy. In both studies, treatment was to continue until disease progression.
Dose adjustments were allowed based on clinical and laboratory findings. Sequential dose reductions to 15 mg daily, 10 mg daily and 5 mg daily were allowed for toxicity (see DOSAGE AND ADMINISTRATION).
Table 8 summarizes the baseline patient and disease characteristics in the two studies. In both studies, baseline demographic and disease-related characteristics were comparable between the lenalidomide/dexamethasone and placebo/dexamethasone groups.
Table 8: Baseline Demographic and Disease-Related Characteristics
| MM-009 (Cutoff: 28 Jun 2005) | MM-010 (Cutoff: 03 Aug 2005) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Lenalidomide / dexamethasone (N=177) | PLACEBO / dexamethasone (N=176) | Lenalidomide / dexamethasone (N=176) | PLACEBO / dexamethasone (N=175) | |||||||||||||
| Patient Characteristics | ||||||||||||||||
Age (years) Median Min, Max | 64.0 36.0, 86.0 | 62.0 37.0, 85.0 | 63.0 33.0, 84.0 | 64.0 40.0, 82.0 | ||||||||||||
Sex Male Female | 106 (59.9%) 71 (40.1%) | 104 (59.1%) 72 (40.9%) | 104 (59.1%) 72 (40.9%) | 103 (58.9%) 72 (41.1%) | ||||||||||||
Race/Ethnicity White Other | 141 (79.7%) 36 (20.3%) | 148 (84.1%) 28 (15.9%) | 172 (97.7%) 4 (2.3%) | 175 (100.0%) 0 (0%) | ||||||||||||
| ECOG Performance Status 0-1 | 157 (88.7%) | 168 (95.5%) | 150 (85.2%) | 144 (82.3%) | ||||||||||||
| Disease Characteristics | ||||||||||||||||
Baseline Multiple Myeloma Stage [b] I II III Missing | 6 (3.4%) 56 (31.6%) 114 (64.4%) 1 (0.6%) | 5 (2.8%) 55 (31.3%) 116 (65.9%) 0 (0%) | 11 (6.3%) 50 (28.4%) 115 (65.3%) 0 (0%) | 8 (4.6%) 57 (32.6%) 110 (62.9%) 0 (0%) | ||||||||||||
| Median (min, max) Baseline β2-microglobulin levels (mg/L) | 3.65 (1.1, 45.0) | 3.30 (1.3, 15.2) | 3.35 (1, 14.4) | 3.25 (1.3, 25.3) | ||||||||||||
| Number of Prior Therapies | ||||||||||||||||
No. of Prior Antimyeloma Therapies 1 ≥ 2 | 68 (38.4%) 109 (61.6%) | 67 (38.1%) 109 (61.9%) | 56 (31.8%) 120 (68.2%) | 57 (32.6%) 118 (67.4%) | ||||||||||||
| Types of Prior Therapies | ||||||||||||||||
| Stem Cell Transplantation | 61.0% | 60.2% | 56.3% | 53.7% | ||||||||||||
| Thalidomide | 41.8% | 45.5% | 30.1% | 38.3% | ||||||||||||
| Dexamethasone | 80.8% | 70.5% | 65.9% | 68.6% | ||||||||||||
| Bortezomib | 10.7% | 11.4% | 4.5% | 4.0% | ||||||||||||
| Melphalan | 33.3% | 30.7% | 56.3% | 52.0% | ||||||||||||
| Doxorubicin | 54.8% | 51.1% | 55.7% | 56.6% | ||||||||||||
[a] More than one category could be selected. Therefore, percentages may total to more than 100%.
[b] Baseline multiple myeloma stage was determined based on the Durie-Salmon staging criteria.
The efficacy and safety of the treatments were monitored at clinic visits that were scheduled at screening/baseline (within 28 days of Day 1 of Cycle 1), on Days 1, 8, and 15 of Cycle 1, on Days 1 and 15 of Cycles 2 and 3, on Day 1 of each subsequent cycle, and at treatment discontinuation. After discontinuation from the study, subjects are contacted every 6 months to obtain data on survival, the cause of death, and subsequent antimyeloma therapy.
The primary efficacy endpoint in both studies was time to progression (TTP). TTP was defined as the time from randomization to the first occurrence of progressive disease or death due to progressive disease. The secondary efficacy endpoints were the myeloma response rate; the time to the first symptomatic skeletal-related event (SRE); the time to the first decrease in the ECOG performance status; and overall survival (OS). The response to therapy was assessed using the Myeloma Response Determination Criteria. The time to SRE was not analyzed due to the small number of observations available.
The median durations of observation at the time of the pre-planned analyses were 17 months for Study MM-009 and 16.5 months for Study MM-010.
Results
Protocol-specified Analysis of TTP (Primary Endpoint)
In both studies, TTP was significantly longer in the lenalidomide /dexamethasone group than in the placebo/dexamethasone group (p < 0.001).
At the time of the preplanned interim analysis, the predetermined stopping criteria for superiority in the primary efficacy endpoint, TTP (as defined in the protocol), had been surpassed, with p<0.001 in favor of the lenalidomide/dexamethasone treatment group. Both studies showed that the combination of lenalidomide/dexamethasone was significantly superior to dexamethasone alone for TTP.
Subjects in the placebo/dexamethasone group were permitted to receive treatment with the lenalidomide/dexamethasone combination after unblinding.
Table 9: Summary of Time to Progression
| Statistics | MM-009 (Cutoff: 28 Jun 2005) | MM-010 (Cutoff: 03 Aug 2005) | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Lenalidomide / dexamethasone (N=177) | PLACEBO / dexamethasone (N=176) | Lenalidomide / dexamethasone (N=176) | PLACEBO / dexamethasone (N=175) | |||||||||||||||||
TTP [a] Progressed Censored | N n (%) n (%) | 177 92 (52.0) 85 (48.0) | 176 132 (75.0) 44 (25.0 | 176 82 (46.6) 94 (53.4) | 175 142 (81.1) 33 (18.9) | |||||||||||||||
| Overall TTP (wk) | Median [b] [95% CI] [c] | 48.1 [36.9, 61.4] | 20.1 [16.7, 23.1] | 48.7 [40.9, 72.1] | 20.1 [18.1, 20.7] | |||||||||||||||
Mean [b] SD Min, Max | 39.0 28.55 0.0, 106.9 | 20.6 19.17 0.0, 93.1 | 38.0 27.08 0.1, 93.4 | 22.9 19.03 0.3, 90.1 | ||||||||||||||||
| Hazard Ratio [95% CI] [d] | 0.354 [0.270, 0.466] | 0.351 [0.266, 0.463] | ||||||||||||||||||
| Log-rank Test p-Value [e] | < 0.001 | < 0.001 | ||||||||||||||||||
NE, not estimable
[a] Time to progression was calculated as the time from randomization to the first occurrence of any of the following events: 1) disease progression based on the myeloma response criteria developed by Bladé et al, 2) discontinuation from the treatment phase due to disease progression according to the investigator whether or not confirmed by the Bladé et al criteria (TTP was measured to the last date of visit), or death due to disease progression during the treatment period (TTP was measured to the date of death if death occurred on or before treatment discontinuation). The TTP was censored at the date of the last response assessment for subjects who 1) had not progressed at the time of the analysis, 2) withdrew from the treatment phase before documented progression, including those who died of causes not related to multiple myeloma, or 3) were given another antimyeloma therapy without documented progression or experienced intolerable adverse events (for these subjects, the date of their last response assessment prior to taking other antimyeloma therapy was used as the censor date).
[b] The median is based on the Kaplan-Meier estimate, and the mean is the univariate mean without adjusting for censoring (i.e., the mean values represent mean TTP documented to date as of the data cutoff date, without consideration of the fact that a substantial number of subjects who had not yet progressed were continuing in the study).
[c] Ninety-five percent confidence interval (CI) about the median overall TTP
[d] Based on a proportional hazards model comparing the hazard functions associated with the treatment groups (lenalidomide / dexamethasone: placebo / dexamethasone)
[e] The p-value is based on a 2-tailed unstratified log-rank test of survival curve differences between the treatment groups.
Superiority of lenalidomide/dexamethasone over placebo/dexamethasone was also observed regardless of gender, age (≤ 65 years and > 65 years), prior therapy (with high-dose chemotherapy and SCT or without such therapy), or the number of prior antimyeloma regimens (1 vs > 1).
Figure 2 depicts the Kaplan-Meier estimates of TTP as of the dates on which the studies were unblinded.
Figure 2: Kaplan-Meier Estimate of Time to Progression
Time to Progression, MM-009 / MM-010
Lenalidomide/Dex vs Placebo/Dex
Data Up to Unblinding (MM009: -28Jun05, MM010: -03Aug05)
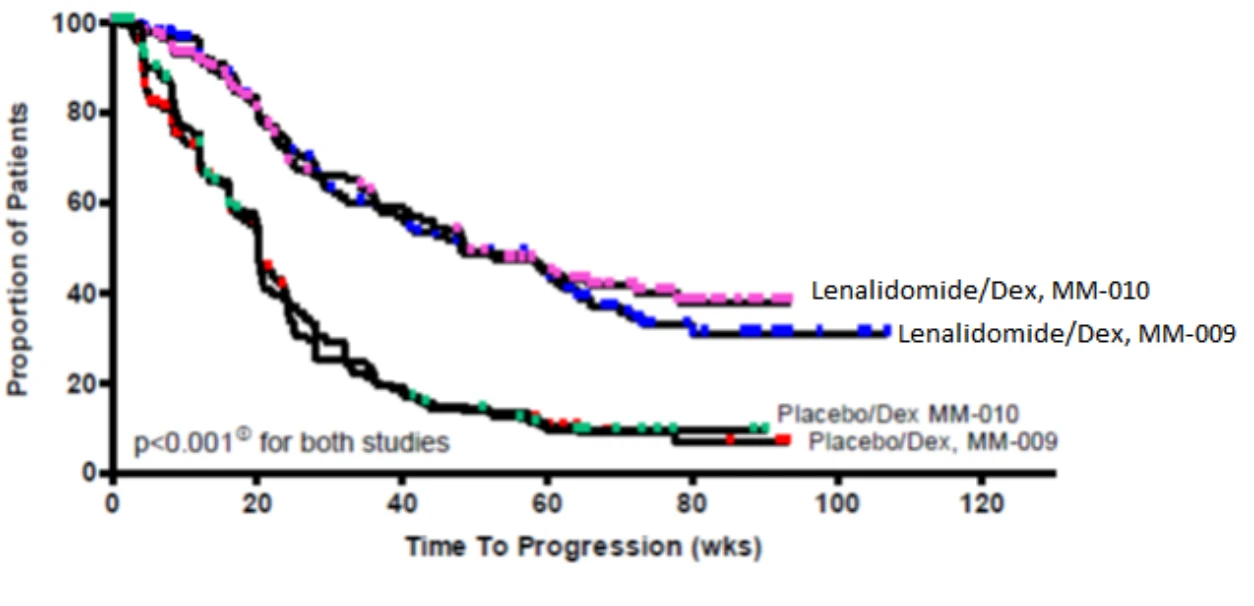
①p-value from log-rank test
Progression Free Survival (PFS) - Sensitivity Analysis)
The analysis of PFS, which differed from the protocol-specified primary TTP analysis in that all deaths, regardless of causality, were considered as events confirmed the results that were observed with the protocol-specified analysis of TTP. Highly significant differences between treatment groups (p < 0.001) in favor of the lenalidomide/dexamethasone combination, were observed in both studies (see Table 10).
Table 10: Summary of Progression-free Survival (Sensitivity Analysis)
| Statistics | MM-009 (Cutoff: 28 Jun 2005) | MM-010 (Cutoff: 03 Aug 2005) | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Lenalidomide / dexamethasone (N=177) | PLACEBO / dexamethasone (N=176) | Lenalidomide / dexamethasone (N=176) | PLACEBO / dexamethasone (N=175) | |||||||||||||||||
PFS [a] Time Progressed Censored | N n (%) n (%) | 177 93 (52.5) 84 (47.5) | 176 134 (76.1) 42 (23.9) | 176 95 (54.0) 81 (46.0) | 175 148 (84.6) 27 (15.4) | |||||||||||||||
| Overall PFS (wk) | Median [b] [95% CI] [c] | 48.0 [36.9, 61.4] | 20.1 [16.4, 23.1] | 44.1 [34.3, 59.0] | 20.1 [16.1, 20.4] | |||||||||||||||
Mean [b] SD Min, Max | 39.1 28.52 0.0, 106.9 | 20.6 19.16 0.0, 93.1 | 37.7 27.11 0.1, 93.4 | 22.9 19.01 0.3, 90.1 | ||||||||||||||||
| Hazard Ratio [95% CI] [d] | 2.820 [2.148, 3.701] | 2.459 [1.891, 3.199] | ||||||||||||||||||
| Log-rank Test p-Value [e] | < 0.001 | < 0.001 | ||||||||||||||||||
NE, not estimable
[a] Calculated as the time from randomization to documented progression or death due to any cause, whichever occurred first. If withdrawal due to adverse events or change of therapy occurred before documented progression or death, then these observations were censored at the last progression assessment date.
[b] The median is based on the Kaplan-Meier estimate, and the mean is the univariate mean without adjusting for censoring (i.e., the mean values represent mean PFS documented to date as of the data cutoff date, without consideration of the fact that a substantial number of subjects who had not yet progressed were continuing in the study).
[c] Ninety-five percent confidence interval (CI) about the median overall PFS.
[d] Based on a proportional hazards model comparing the hazard functions associated with the treatment groups (Lenalidomide / dexamethasone:placebo / dexamethasone)
[e] The p-value is based on a 1-tailed unstratified log-rank test of survival curve differences between the treatment groups.
Myeloma Response Rate (Secondary Endpoint)
In both studies, the myeloma response rates were significantly higher in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group both for the overall comparison of response categories (p < 0.001) and for the dichotomous comparison of Complete Response (CR) + Remission Response (RR) + Partial Response (PR)(p < 0.001) (see Table 11). The overall response rates in Study 009 were consistent with those in Study 010, with 61.0% (108/177) of the lenalidomide/dexamethasone-treated subjects in Study 009 and 60.2% (106/176) of the lenalidomide /dexamethasone-treated subjects in Study 010 achieving a CR, RR plus PR.
Table 11: Summary of Myeloma Response Rates Based on Best Response Assessments (Studies MM-009 and MM-010)
| Response [a, b] | Study MM-009 (Cutoff: 28 Jun 2005) | Study MM-010 (Cutoff: 03 Aug 2005) | ||
|---|---|---|---|---|
Lenalidomide / dexamethasone (N=177) | PLACEBO / dexamethasone (N=176) | Lenalidomide / dexamethasone (N=176) | PLACEBO / dexamethasone (N=175) | |
| Complete Response (CR) | 25 (14.1%) [g] | 1 (0.6%) | 28 (15.9%) [g] | 6 (3.4%) |
| Partial Response (PR) | 31 (17.5%) | 18 (10.2%) | 32 (18.2%) | 20 (11.4%) |
| Stable Disease (SD) | 54 (30.5%) | 102 (58.0%) | 53 (30.1%) | 97 (55.4%) |
| Progressive Disease (PD) | 5 (2.8%) | 25 (14.2%) | 3 (1.7%) | 25 (14.3%) |
| Not Evaluable (NE) [c] | 10 (5.6%) | 14 (8.0%) | 14 (8.0%) | 11 (6.3%) |
| p-value [d] | < 0.001 | < 0.001 | ||
| Dichotomized Response | ||||
| CR, RR, or PR | 108 (61.0%) | 35 (19.9%) | 106 (60.2%) | 42 (24.0%) |
| SD, PD, or NE | 69 (39.0%) | 141 (80.1%) | 70 (39.8%) | 133 (76.0%) |
| p-value [e] | < 0.001 | < 0.001 | ||
| Odds Ratio [f] [95% CI] | 6.31 [3.91, 10.17] | 4.80 [3.03, 7.59] | ||
[a] Response is based on the review of all myeloma assessment data using Bladé et al criteria.
[b] Response is the highest assessment of response during the treatment phase of the study.
[c] Includes subjects who did not have any response assessment data as of the data cutoff date and those whose only assessment was “response not evaluable.” This category was not included in the Wilcoxon rank sum test.
[d] Probability from Wilcoxon rank sum test
[e] Probability from continuity-corrected Pearson chi square test
[f] Odds ratio (lenalidomide: placebo)
[g] Significantly higher in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group (p < 0.003, continuity-corrected Pearson chi square test)
Based on subgroup analyses, the myeloma response rate (CR + RR + PR) and CR rate were significantly higher in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group regardless of gender, age (≤ 65 years or > 65 years), prior therapy
(with high-dose chemotherapy and SCT or without such therapy; or number of prior antimyeloma regimens (1 vs ≥ 1). The myeloma response rate (CR + RR + PR) and the CR rate were also significantly higher in the lenalidomide/dexamethasone group than in the placebo/dexamethasone group both in subjects who had a baseline serum β2-microglobulin level of ≤ 2.5 mg/L and in those who had a baseline β2-microglobulin level of > 2.5 mg/L.
Overall Survival (Secondary endpoint)
Based on pooled data from Study 009 and Study 010 at the time of un-blinding, overall survival (OS) was significantly longer (p<0.001); among the lenalidomide /dexamethasone-treated subjects than among the placebo/dexamethasone -treated subjects. Subjects in the placebo/dexamethasone group were permitted to receive treatment with the lenalidomide/dexamethasone combination after un-blinding. As of January 2007, OS was significantly longer (p=0.015) among the lenalidomide /dexamethasone-treated subjects than among the placebo/dexamethasone -treated subjects (see Table 12), however the data are confounded by the effects of the crossover of placebo/dexamethasone subjects to lenalidomide. A total of 146 patients (96 from Study MM-009 and 50 from Study MM-010) rolled over to receive lenalidomide before study un-blinding. After study un-blinding, a total of 19 patients (5 from Study MM-009 and 14 from Study MM-010) crossed over to receive lenalidomide/dexamethasone.
Table 12: Summary of Overall Survival as of January 2007: Intent-To-Treat Population
Overall Survival (OS) Statistics | Pooled Data | |
|---|---|---|
Lenalidomide / dexamethasone N=353 | PLACEBO / dexamethasone N=351 | |
| Died n (%) | 152 (43.1) | 180 (51.3) |
Median OS time since randomization, weeks [a] 95% CI [b] Mean ± SD Min, Max | 149.7 [141.6, NE] 101.5 ± 51.39 1.1, 183.1 | 133.3 [111.0, 151.7] 92.4 ± 53.86 0.0, 187.9 |
| Hazard rate ratio [c] | 0.765 [0.616, 0.949] | |
| p-value [d] | 0.015 | |
| 3-yr survival rate (95% CI) | 47% (40-54%) | 43% (37-49%) |
Notes: The median in this table is based on Kaplan-Meier estimate, and the mean is the univariate mean without adjusting for censoring.
NE= Not Estimable
[a] For subjects who died during the follow-up phase and whose death dates are not available, the follow-up visit dates are used as the event date.
[b] 95% confidence intervals about the median survival time.
[c] Based on a proportional hazards model comparing the hazard functions associated with the treatment groups (Lenalidomide / dexamethasone: Placebo / dexamethasone)
[d] The p-value is based on a two-tailed unstratified log rank test of survival curve differences between the treatment groups.
Figure 3: Overall Survival Data from CC-5013-MM-009; January 2007
Overall Survival, MM-009
Lenalidomide /Dex vs Placebo / Dex
Data Up to January 2007
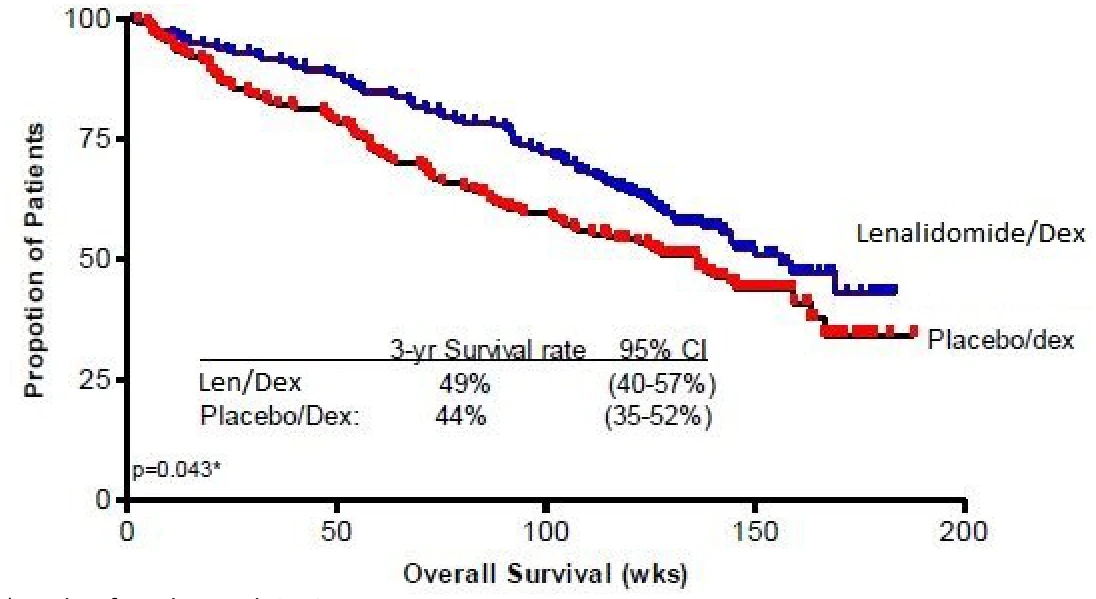
*p-value from log-rank test
Figure 4: Overall Survival Data from CC-5013-MM-010; January 2007
Overall Survival, MM-010
Lenalidomide / Dex vs Placebo / Dex
Data Up to January 2007
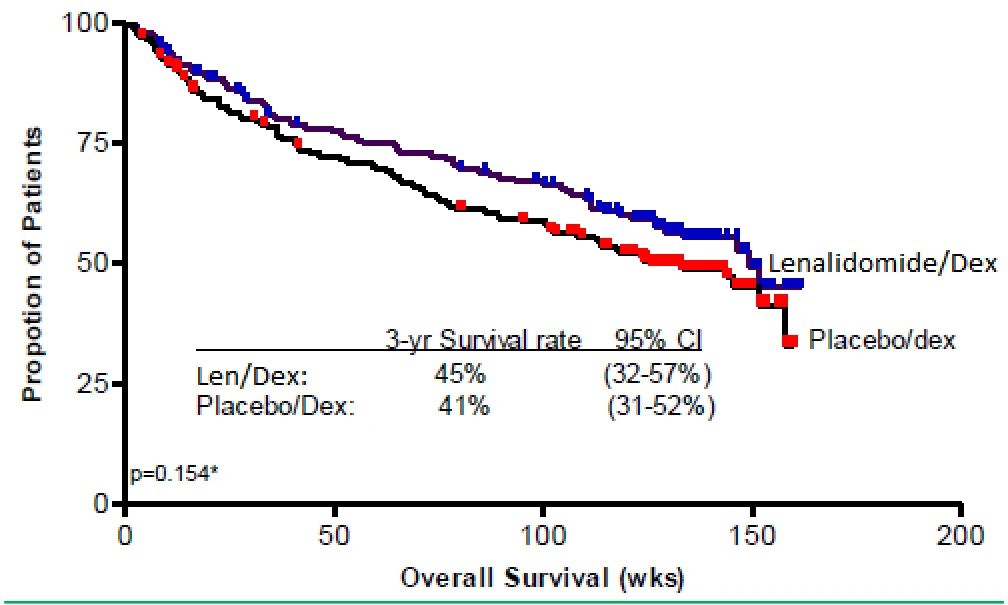
*p-value from log-rank test
Time to First Worsening of ECOG Performance Status (Secondary Endpoint)
The time to the first worsening of the ECOG performance status score was significantly longer for the lenalidomide/dexamethasone-treated subjects than for the placebo/dexamethasone-treated subjects in Study 009 (p = 0.012). No significant difference in the time to first worsening in the ECOG performance status score was observed between the lenalidomide/dexamethasone and placebo/dexamethasone groups in Study 010.
DETAILED PHARMACOLOGY
Clinical Pharmacokinetics
The pharmacokinetic profile of lenalidomide has been evaluated in Caucasian, Japanese, and Chinese patients with previously treated multiple myeloma (MM) (see Table 13).
Table 13: Single-dose Pharmacokinetic Parameters of Lenalidomide in Patients with Previously Treated MM
| Parameter | Multiple Myeloma (Lenalidomide = 25 mg, Clcr ≥ 60 mL/min) | ||
|---|---|---|---|
Caucasiana (N = 34) | Japanesea (N = 12) | Chinese (N = 9) | |
| AUC∞ (ng•h/mL) | 2124 (28.6) | 2305 (23.7) | 2202 (30.6) |
| Cmax (ng/mL) | 487 (35.0) | 572 (33.2) | 596 (30.2) |
| Tmax (h) | 1.0 (0.4-4.0) | 1.0 (0.4-2.0) | 0.93 (0.5-1.0) |
| CL/F (mL/min) | 196 (28.7) | 181 (23.7) | 184 (30.7) |
| t1/2 (h) | 3.18 (20.7) | 2.70 (19.3) | 3.18 (39.0) |
Median (minimum – maximum) data are presented for Tmax and geometric mean (CV%) data are presented for other parameters. Only patients with similar renal function (CLcr > 60 mL/min) are included.
AUC∞ = AUC from time zero extrapolated to infinity; Cmax = maximum concentration; CL/F = apparent total clearance ; t1/2 = terminal half-life; Tmax = time to reach Cmax
aAUC∞ and Cmax are normalized to the level at 25 mg.
Drug Interactions
The pharmacokinetics of lenalidomide (25 mg/day) when administered alone or in combination with dexamethasone (40 mg/day) was evaluated in Japanese and Chinese subjects with previously treated multiple myeloma (see Table 14). Dexamethasone had no effect on the pharmacokinetics of lenalidomide.
Table 14 Summary of Pharmacokinetic Parameters of Lenalidomide Alone or in Combination with Dexamethasone in Subjects with Previously Treated MM
| Parameter | Japanese Subjectsa | Chinese Subjectsb | ||||
Len 25 mg Day 1 (N=6) | Len + Dex Day 12 (N=6) | Len 25 mg Day 7 (N=11) | Len + Dex Day 8 (N=10) | |||
| Cmax (ng/mL) | 474 (27.1) | 433 (46.1) | 478 (19.3) | 494 (19.9) |
| tmax (h) | 1.70 (1.00-1.97) | 2.76 (0.53-4.0) | 1.5 (0.5-3.1) | 1.00 (0.50-2.98) |
AUCτ (ng• h/mL) | 2177 (12.6) | 1890 (17.4) | 2117 (43.7) | 2093 (41.2) |
| t1/2 (h) | 2.56 (14.0) | 2.55 (23.0) | 2.79 (32.6) | 3.08 (46.8) |
| CL/F (mL/min) | 191 (12.8) | 221 (18.3) | 195 (45.5) | 193 (42.6) |
Median (minimum-maximum) data are presented for Tmax and geometric mean (CV%) data are presented for other parameters. AUC = area under the concentration versus time curve from the time zero until the end of the dosing interval (τ=24); Cmax = maximum concentration; CL/F = apparent total plasma clearance when dosed orally; t1/2 = terminal half life
a Lenalidomide was administered at 25 mg daily on Days 1 and 3-12 and dexamethasone at 40 mg daily on Days 2-4 and 9-12.
b Lenalidomide was administered at 25 mg daily on Days 1-8 and dexamethasone at 40 mg on Day 8.
Non-Clinical Pharmacology
Lenalidomide is a potent and orally effective antineoplastic, immunomodulatory, and antiangiogenic drug. The pharmacological properties of lenalidomide were characterized in both in vitro and in vivo non-GLP studies examining the potential to produce any adverse secondary pharmacological effects. The results of these studies demonstrate that lenalidomide induces fetal hemoglobin expression upon CD34+ hematopoietic stem cell differentiation in a model of erythroid progenitor differentiation; inhibits proliferation of various hematopoietic tumor cell lines and multiple myeloma (MM) plasma tumor cells; and inhibits angiogenesis in vitro by blocking the formation of microvessels and endothelial cell tubes, as well as the migration and adhesion of endothelial cells and in vivo by reducing the microvessel density in the rat mesenteric window model and in the beige-nude-xid mouse MM tumor model. In addition, lenalidomide stimulates T-cell proliferation and interleukin (IL)-2 and interferon-gamma production; and increases natural killer (NK) and NK T cell number and activity; and inhibits the secretion of pro-inflammatory cytokines including tumor necrosis factor-alpha, IL-1β, IL-6 and IL-12, and increases the secretion of anti-inflammatory cytokine IL-10 from peripheral blood mononuclear cells.
Some of the cellular effects listed above (T cell stimulation, inhibition of tumor cell proliferation, and inhibition of endothelial cell migration) are associated with modulation of the Akt pathway, suggesting that this core signaling pathway may be a key molecular target of lenalidomide.
In rats and monkeys, lenalidomide is cleared at a moderate rate from the systemic circulation, and is rapidly absorbed, with oral bioavailability of ≥ 50% in rats and monkeys. In animals, systemic exposure increased with increasing doses, with no notable accumulation on multiple dosing of lenalidomide.
The plasma protein binding of lenalidomide is low (19 to 29% bound) in nonclinical species as well as humans. 14C-Lenalidomide-derived radioactivity is extensively distributed into tissues in rats. Very limited distribution of radioactivity occurs into the central nervous system (less than 5% of levels in blood).
Lenalidomide is not subject to cytochrome P450 mediated metabolism in vitro. It undergoes hydrolysis in aqueous media, and animal and human plasma. The enantiomers of lenalidomide undergo facile interconversion in animal and human plasma in vitro.
The excretion of radioactivity following oral dosing of 14C-lenalidomide to rats and monkeys is rapid and occurs via both the urine and feces. In both rats and monkeys, the major component of the excreted radioactivity is the parent compound (50 to 58% of the dose). The remaining radioactive dose is excreted as multiple metabolites comprising isomeric forms of hydrolytic metabolites (5 to 10% of the dose), an N-acetyl conjugate (less than 3% of the dose) and isomers of a glucose conjugate (less than 13% of the dose). Thus, multiple clearance mechanisms contribute to the overall elimination of lenalidomide in animal models.
Lenalidomide does not inhibit or induce cytochrome P450 isoforms in vitro, and hence is not likely to precipitate drug-drug interactions when administered with cytochrome P450 substrates. In vivo in both rats and monkeys, chronic administration of lenalidomide did not result in the induction of cytochrome P450 enzymes. In vitro lenalidomide is a weak substrate, but is not an inhibitor of P-glycoprotein. Hence clinically relevant drug-drug interactions between lenalidomide and P-glycoprotein substrates or inhibitors are unlikely.
Non-Clinical Safety Pharmacology
Results of safety pharmacology studies have shown that lenalidomide did not induce behavioral or autonomic changes when administered orally to male rats at doses up to 2000 mg/kg, did not produce major inhibition of the cloned human cardiac potassium channel (hERG) (IC50 > 786.7 mcM) in vitro, and did not induce any biologically significant cardiovascular or respiratory changes when administered intravenously to anesthetized dogs at doses up to 20 mg/kg.
TOXICOLOGY
| Study Title | Findings |
|---|---|
| Single dose intravenous toxicity study in the mouse | No deaths after a single intravenous administration of 40 mg/kg were observed in mice. |
| Single dose oral toxicity study in the mouse | No deaths after a single oral dose of 2000 mg/kg were observed in mice. |
| Single dose intravenous toxicity study in the rat | No deaths after a single intravenous administration of 40 mg/kg were observed in rats. |
| Single dose oral toxicity study in the rat | No deaths after a single oral dose of 2000 mg/kg were observed in rats. |
| Study Title | Findings |
|---|---|
| 7 day oral (gavage) range-finding toxicity study in the mouse | High dose females exhibited slightly elevated liver weights (p<0.05). NOAEL = 1000 mg/kg/day. |
| 7 day oral (gavage) range finding toxicity study in the rat | Decreased red blood cell indices in treated males. Increased urea and creatinine in treated males at 500 and 2000 mg/kg. Increased kidney weights in males at 500 and 2000 mg/kg. NOAEL = < 500 mg/kg/day. |
| 28 day oral (gavage) toxicity study in the rat | Bodyweight and feed consumption decreased in high dose males. Unidentified crystals were noted in the urine of treated animals. At week 4, increased incidence of proteinuria and hematuria in high dose males. White powder deposit was noted in the urine of the mid and high dose animals. Moderate to severe tubular necrosis or nephropathy noted in the high dose rats. Slight decrease in red blood cell parameters for high dose males. NOAEL = 300 mg/kg/day. |
| 13 week oral (gavage) toxicity study in the rat | Decreased body weight gains and unidentified crystals in the urine at the mid and high dose. NOAEL = 75 mg/kg/day. |
| 26 week (with a 4 week treatment-free recovery period) oral (gavage administration) toxicity study in the rat | Male and female rats were administered 0, 75, 150 or 300 mg/kg/day for 26 weeks. In this study, there were 3 non-treatment related deaths; 1 male at 300 mg/kg and 2 females from control and 150 mg/kg groups. No treatment-related clinical signs were observed during the treatment and treatment-free periods. Hematology, clinical chemistry, urinalysis, ophthalmoscopic findings were unaffected by treatment. At the end of treatment, there were slight decreases of 16% and 9% in group mean unadjusted liver weight and organ to body weight ratio in males dosed with 300 mg/kg/day. Microscopically, a treatment-related increase in the incidence of pelvic mineralization was seen in the kidney at all doses. After 4 weeks, recovery from this effect was observed in the high dose group. The NOAEL was 75 mg/kg/day. |
| 28 day oral (gavage) toxicity study in the monkey. | One animal sacrificed in moribund condition. Animal exhibited increased urea, creatinine & bilirubin. Lesions in bone marrow & lymphocytic system, kidneys, GI tract & liver. Minor atrophy of the thymus, spleen and peripheral lymph nodes and altered hematopoiesis were noted. NOAEL was not achieved. |
| 28 day oral (gavage) toxicity study in the monkey | No treatment related effects. NOAEL = 2 mg/kg/day. |
| 13 week oral (gavage) toxicity study in the monkey | The top dose of 2/mg/kg/day was the NOAEL. Evidence of pharmacodynamic activity was noted at all dose levels. |
| Study Title | Findings |
|---|---|
| 52 week oral (gavage administration) toxicity study in the monkey | A number of animals administered 4 and 6 mg/kg/day were terminated early due to toxicity on Day 135. In these animals, treatment-related findings consisted of severely reduced RBC, WBC, and platelet counts, hemorrhage in multiple organs, gastrointestinal tract inflammation and lymphoid and bone marrow atrophy. For animals administered 1 and 2 mg/kg/day, mild, but inconsistent, suppression of white blood cell count at 2 mg/kg/day was observed. Histology at 52 weeks showed atrophy of the thymus at both doses. After 7 weeks of recovery, platelet and WBC counts were similar to control; the effects on the thymus were partially reversed. The NOAEL in this study was 1 mg/kg/day. |
| Fertility and early Embryonic Development | A fertility and early embryonic development study in rats, with administration of lenalidomide up to 500 mg/kg, produced no parental toxicity and no adverse effects on fertility. |
| Embryo-fetal development studies: | Embryofetal developmental toxicity studies were conducted in rats, rabbits and monkeys. In monkeys, malformations were observed in the offspring of female monkeys who received lenalidomide doses as low as 0.5 mg/kg/day during pregnancy. Exposure in monkeys at this dose (AUC of 378 ng•hr/mL) was 0.17-times the exposure from a human clinical dose of 25 mg/day (AUC of 2215 ng•hr/mL). The observed malformations ranged from stiff and slightly malrotated hindlimbs at 0.5 mg/kg/day lenalidomide up to severe external malformations, such as bent, shortened, malformed, malrotated, and/or absent part of the extremities, oligo– or polydactyly at 4 mg/kg/day lenalidomide. These external malformations had correlated skeletal finding and were similar to those seen with the positive control thalidomide treatment. In rabbits, the maternal and developmental NOAELs for lenalidomide were 3 mg/kg/day. Exposure of rabbits at this dose (AUC of 2858 ng•hr/mL) was 2.3 fold higher than in patients administered 10 mg of lenalidomide based on AUC. Exposure in patients administered 25 mg of lenalidomide was approximately the same as in rabbits at the NOAEL dose based on AUC. Lenalidomide has been shown to have an embryocidal effect in rabbits at a dose of 50 mg/kg. Developmental toxicity at the 10 and 20 mg/kg/day dose levels was characterized by slightly reduced fetal body weights, increased incidences of post implantation loss, and gross external findings in the fetuses associated with morbidity and pharmacotoxic effects of lenalidomide (purple discoloration of the skin on the entire body). |
| Study Title | Findings |
|---|---|
| Pre- and Post-Natal Development: | A pre- and post-natal development study in rats revealed few adverse effects in the offspring of female rats treated with lenalidomide at doses up to 500 mg/kg (approximately 600 times and 240 times the human dose of 10 and 25 mg, respectively based on body surface area). Exposures to lenalidomide at these doses were ≥ 128-fold and 50-fold higher than in patients administered 10 mg and 25 mg, respectively based on AUC. The male offspring exhibited slightly delayed sexual maturation, and the female offspring had slightly lower body weight gains during gestation when bred to male offspring. |
| Carcinogenicity | Carcinogenicity studies with lenalidomide have not been conducted. |
| Mutagenicity | Lenalidomide did not induce mutation in the Ames test, chromosome aberrations in cultured human peripheral blood lymphocytes, or mutation at the thymidine kinase (tk) locus of mouse lymphoma L5178Y cells. Lenalidomide did not increase morphological transformation in Syrian Hamster Embryo assay or induce micronuclei in the polychromatic erythrocytes of the bone marrow of male rats. |
REFERENCES
- 1. Amin RP, Fuchs A, Christian MS, Latriano L, Weinbauer GP, Bryan P et al. An embryo-fetal developmental toxicity study of lenalidomide in cynomolgus monkeys. Birth Defects Res (Part a) 2009; 85:435.
- 2. Benboubker L, Dimopoulos MA, Dispenzieri A, et al. Lenalidomide and dexamethasone in transplant-ineligible patients with myeloma. N Engl J Med. 2014;37:906-17.
- 3. Bladé, J, Samson, D, Reece, D, Apperley, J, Björkstrand, B, Gahrton, G, et al. Criteria for evaluating disease response and progression in subjects with multiple myeloma treated by high-dose therapy and haemopoietic stem cell transplant. Br J Haematol. 1998; 102:1115-1123.
- 4. Blom JW, Doggen CJM, Osanto S, Rosendaal, FR. Malignancies, prothrombotic mutations, and the risk of venous Thrombosis. JAMA 2005 (Feb 9); 293(6):715-722.
- 5. Dimopoulos M, Spencer A, Attal M, Prince HM, Harousseau J, Dmoszynska A et al. Lenalidomide plus dexamethasone for relapsed or refractory multiple myeloma. N Engl J Med 2007; 357:2123-32.
- 6. Dimopoulos M et al. The efficacy and safety of lenalidomide plus dexamethasone in relapsed and/or refractory multiple myeloma patients with impaired renal function. Cancer 2010; 116:3807-14.
- 7. Dimopoulos M et al. Impact of lenalidomide dose on progression-free survival in patients with relapsed or refractory multiple myeloma. Leukemia 2011; 25: 1620–1626.
- 8. Dimopoulos M et al. Optimizing the use of lenalidomide in relapsed or refractory multiple myeloma: consensus statement. Leukemia 2011; 25: 749-760.
- 9. Dredge K, Horsfall R, Robinson SP, et al. Orally administered lenalidomide (CC-5013) is anti-angiogenic in vivo and inhibits endothelial cell migration and Akt phosphorylation in vitro. Microvasc Res. 2005; 69(1-2):56-63.
- 10. Durie BGM, Salmon SE. The current status and future prospects of treatment for multiple myeloma. Clinics Haematol. 1982; 11:181-210.
- 11. Harousseau JL et al. The quality of response to lenalidomide plus dexamethasone is associated with improved clinical outcomes in patients with relapsed or refractory multiple myeloma. Haematologica 2010; 95(10):2–8.
- 12. Linenberger ML, Wittkowsky AK. Thromboembolic complications of malignancy. Part 1: risks. Oncology. 2005a (June):853-861.
- 13. Munshi NC, Tricot G, Barlogie B. Plasma cell neoplasms, in DeVita VT, Hellman S, Rosenberg SA (ed): Cancer: Principles & Practice of Oncology, 6th edition, Philadelphia, PA. Lippincott Williams & Wilkins, 2001, pp 2465-2499.
- 14. Palumbo A et al. Lenalidomide in combination with dexamethasone for the treatment of relapsed or refractory multiple myeloma. Blood Reviews. 2009; 23:87–93.
- 15. Rajkumar S et al. Lenalidomide plus high-dose dexamethasone versus lenalidomide plus low-dose dexamethasone as initial therapy for newly diagnosed multiple myeloma: an open-label randomised controlled trial. Lancet Oncol 2010; 11: 29-37.
- 16. Reece D et al. Influence of cytogenetics in patients with relapsed or refractory multiple myeloma treated with lenalidomide plus dexamethasone: adverse effect of deletion 17p13. Blood 2009; 114: 522-525.
- 17. Richardson PG, Schlossman RL, Weller E, Hideshima T, Mitsiades C, Davies F, et al. Immunomodulatory drug CC-5013 overcomes drug resistance and is well tolerated in patients with relapsed multiple myeloma. Blood 2002;100(9): 3063–3067.
- 18. San Miguel JF et al. Effects of lenalidomide and dexamethasone treatment duration on survival in patients with relapsed or refractory multiple myeloma treated with lenalidomide and dexamethasone. Clin Lymph Myeloma Leuk 2011: 11 (1): 38-43.
- 19. Stadtmauer EA et al. Lenalidomide in combination with dexamethasone at first relapse in comparison with its use as later salvage therapy in relapsed or refractory multiple myeloma. Eur J Haematol 2009; 82:426–32.
- 20. Thornburg A, Abonour R, Smith P, Knox K, Twigg H. Hypersensitivity Pneumonitis-Like Syndrome Associated With the Use of Lenalidomide. Chest 2007; 131: 1572-1574.
- 21. Wang M et al. Lenalidomide plus dexamethasone is more effective than dexamethasone alone in patients with relapsed or refractory multiple myeloma regardless of prior thalidomide exposure. Blood 2008; 112(12): 4445-4451.
- 22. Weber DM, Chen C, Niesvizky R, Wang M, Belch A, Stadtmauer EA et al. Lenalidomide plus dexamethasone for relapsed multiple myeloma in North America. N Engl J Med 2007; 357:2133-42.
- 23. Product Monograph - REVLIMID® (lenalidomide capsules): Celgene Inc., Mississauga, Ontario Canada L5N 7Y2. Date of Revision: August 20, 2019. Control Number: 229241.