


Product Monograph - Leukeran
RECENT MAJOR LABEL CHANGES
| Dosage and Administration, Recommended Dose and Dosage Adjustment (4.1) | 08/2017 |
| Warnings and Precautions (7) | 08/2017 |
TABLE OF CONTENTS
PART I: HEALTH PROFESSIONAL INFORMATION ..........................................................4
1 INDICATIONS ..................................................................................................................4
1.1 Pediatrics ....................................................................................................................4
1.2 Geriatrics ....................................................................................................................4
2 CONTRAINDICATIONS .................................................................................................4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................4
4 DOSAGE AND ADMINISTRATION .............................................................................5
4.1 Dosing Considerations ...............................................................................................5
4.2 Recommended Dose and Dosage Adjustment ...........................................................5
5 OVERDOSAGE .................................................................................................................6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................6
7 WARNINGS AND PRECAUTIONS ...............................................................................7
7.1 Special Populations ....................................................................................................9
7.1.1 Pregnant Women ................................................................................................... 9
7.1.2 Breast-feeding ....................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................... 9
7.1.4 Geriatrics ............................................................................................................... 9
8 ADVERSE REACTIONS ..................................................................................................9
8.1 Adverse Reaction Overview ......................................................................................9
8.2 Clinical Trial Adverse Reactions ...............................................................................9
9 DRUG INTERACTIONS ................................................................................................11
9.1 Serious Drug Interactions Box .................................................................................11
9.2 Overview ..................................................................................................................11
10 ACTION AND CLINICAL PHARMACOLOGY ........................................................11
10.1 Mechanism of Action ...........................................................................................11
10.2 Pharmacodynamics...............................................................................................11
10.3 Pharmacokinetics .................................................................................................12
11 STORAGE, STABILITY AND DISPOSAL .................................................................13
12 SPECIAL HANDLING INSTRUCTIONS ....................................................................13
PART II: SCIENTIFIC INFORMATION ................................................................................14
13 PHARMACEUTICAL INFORMATION ......................................................................14
14 NON-CLINICAL TOXICOLOGY ................................................................................14
PART III: PATIENT MEDICATION INFORMATION ........................................................15
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
LEUKERAN® (chlorambucil) is indicated as monotherapy in the treatment of chronic lymphocytic leukemia. It is also indicated as monotherapy or in combination with other agents in non-Hodgkin’s lymphomas including follicular lymphoma, indolent lymphoma, MALT-lymphoma, mantle-cell lymphoma; Waldenström’s macroglobulinemia and Hodgkin's disease. It is not curative but produces remissions.
1.1 Pediatrics
Pediatrics (< 18 years of age):
The safety and effectiveness in children have not been established.
1.2 Geriatrics
Geriatrics (> 65 years of age):
No data is available.
2 CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the product monograph.
- LEUKERAN® (chlorambucil) should not be administered to patients who are resistant to the drug or who have developed hypersensitivity to it. There may be cross-hypersensitivity (skin rash) between chlorambucil and other alkylating agents.
- Chlorambucil should not be used within four weeks of a full course of radiation or chemotherapy.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
LEUKERAN® (Chlorambucil) is a potent drug product and should be used only by physicians experienced with cancer chemotherapeutic drugs.
- Myelosupression, including irreversible bone marrow failure (see WARNINGS AND PRECAUTIONS/Hematologic).
- Seizures (see WARNINGS AND PRECAUTIONS/Neurologic)
- Skin toxicity, including Stevens-Johnson syndrome and toxic epidermal necrolysis (see WARNINGS AND PRECAUTIONS/Skin)
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Geriatrics: While clinical experience has not revealed age-related differences in response, drug dosage should be titrated carefully in older patients, usually initiating therapy at the low end of the dosage range (See ACTION AND CLINICAL PHARMACOLOGY/Pharmacokinetics/Special Populations and Conditions).
- Hepatic Insufficiency: Since chlorambucil is primarily metabolized in the liver, dose reduction should be considered in patients with severe hepatic impairment. However, there are insufficient data in patients with hepatic impairment to provide a specific dosing recommendation (See ACTION AND CLINICAL PHARMACOLOGY/Pharmacokinetics/Special Populations and Conditions).
4.2 Recommended Dose and Dosage Adjustment
Chlorambucil tablets are administered orally and should be taken daily on an empty stomach (at least one hour before meals or three hours after meals).
Chronic Lymphocytic Leukemia
Treatment with LEUKERAN® (chlorambucil) is usually started after the patient has developed symptoms or when there is evidence of impaired bone marrow function (but not marrow failure) as indicated by the peripheral blood count.
Initially, LEUKERAN® is given at the dose of 0.15 mg/kg/day until the total leukocyte count is formed to 10 000 per μL. Treatment may be resumed four weeks after the end of the first course and continued at a dosage of 0.1 mg/kg/day.
In a proportion of patients, usually after about two years of treatment, the blood leukocyte count is reduced to the normal range, enlarged spleen and lymph nodes become impalpable and the proportion of lymphocytes in the bone marrow is reduced to less than 20%.
Patients with evidence of bone marrow failure should first be treated with prednisolone and evidence of marrow regeneration should be obtained before commencing treatment with LEUKERAN®.
Intermittent high dose therapy has been compared with daily chlorambucil but no significant difference in therapeutic response or frequency of side effects was observed between the two treatment groups.
Non-Hodgkin's Lymphoma
Used as a single agent, the usual dosage is 0.1 to 0.2 mg/kg/day for 4-8 weeks initially. Maintenance therapy is then given either by a reduced daily dosage or intermittent courses of treatment.
LEUKERAN® is useful in the management of patients with advanced lymphocytic lymphoma and those who have relapsed after radiotherapy.
There is no significant difference in the overall response rate obtained with chlorambucil as a single agent and combination chemotherapy in patients with advanced non-Hodgkin's lymphocytic lymphoma.
Hodgkin's Disease
Used as a single agent in the palliative treatment of advanced disease, a typical dosage is 0.2 mg/kg/day for 4-8 weeks. LEUKERAN® is usually included in combination therapy and a number of regimes have been used. LEUKERAN® may also be used as an alternative to nitrogen mustard with a reduction in toxicity but similar therapy results.
Waldenström's Macroglobulinaemia
LEUKERAN® is the one of the treatment choices in this indication. The following dosing regimen is recommended:
Induction: 0.1-0.2 mg/kg/day PO
Maintenance: 0.03-0.1 mg/kg/day PO
Health Canada has not authorized an indication for pediatric (<18 years of age) use. (see INDICATIONS/Pediatrics)
5 OVERDOSAGE
Reversible pancytopenia was the main finding of inadvertent overdose of chlorambucil. Neurological toxicity ranging from agitated behaviour and ataxia to multiple grand mal seizures has also occurred. As there is no known antidote, the blood picture should be closely monitored and general supportive measures should be instituted together with appropriate blood transfusion if necessary. Chlorambucil is not dialyzable. The physician should consider contacting a poison centre for additional information on the treatment of any overdose.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | tablet / 2 mg | anhydrous lactose, colloidal silicon dioxide, hydroxypropyl methylcellulose, macrogol, microcrystalline cellulose, stearic acid, synthetic red iron oxide, synthetic yellow iron oxide and titanium dioxide |
LEUKERAN® (chlorambucil) Tablets 2 mg are brown film-coated, round, biconvex tablets engraved "GX EG3" on one face and "L" on the other face. Available in bottles of 25 tablets.
Each LEUKERAN® (chlorambucil) Tablet contains 2 mg chlorambucil and the non-medicinal ingredients anhydrous lactose, colloidal silicon dioxide, microcrystalline cellulose and stearic acid. The tablet coating contains: hydroxypropyl methylcellulose, macrogol, synthetic red iron oxide, synthetic yellow iron oxide and titanium dioxide.
7 WARNINGS AND PRECAUTIONS
Please see the Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information.
General
LEUKERAN® (chlorambucil), a derivative of nitrogen mustard, is a potent drug. It is for use only under the direction of physicians experienced in the administration of cancer chemotherapeutic drugs.
Patients who will potentially have autologous stem cell transplantation should not be treated with chlorambucil long term.
When lymphocytic infiltration of the bone marrow is present, or the bone marrow is hypoplastic, the daily dose should not exceed 0.1 mg/kg body weight.
Carcinogenesis and Mutagenesis
Acute secondary hematologic malignancies (especially leukemia and myelodysplastic syndrome) have been reported, particularly after long term treatment (see ADVERSE REACTIONS).
A comparison of patients with ovarian cancer who received alkylating agents with those who did not, showed that the use of alkylating agents including chlorambucil, significantly increased the incidence of acute leukemia.
Acute myelogenous leukemia has been reported in a small proportion of patients receiving chlorambucil as long-term adjuvant therapy for breast cancer.
The leukemogenic risk must be balanced against the potential therapeutic benefit when considering the use of chlorambucil.
Driving and Operating Machinery
Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Hematologic
Blood counts should be taken once or twice weekly. Discontinue or reduce the dosage upon evidence of abnormal depression of the bone marrow (see Monitoring and Laboratory Tests).
Hepatic/Biliary/Pancreatic
Consideration should be given to dose reduction in patients with gross hepatic dysfunction.
Immune
Immunisation using a live organism vaccine has a potential to cause infection in immunocompromised hosts. Therefore, immunisations with live organism vaccines are not recommended.
Monitoring and Laboratory Tests
Since LEUKERAN® (chlorambucil) is capable of producing irreversible bone marrow depression, blood counts should be monitored once or twice weekly in patients under treatment.
At therapeutic dosage, LEUKERAN® depresses lymphocytes and has less effect on neutrophil and platelet counts and on hemoglobin levels. Discontinuation of LEUKERAN® is not necessary at the first sign of a fall in neutrophils but it must be remembered that the fall may continue for 10 days or more after the last dose.
Neurologic
Patients with nephrotic syndrome, patients prescribed high pulse dose regimens and patients with a history of seizure disorder, should be closely monitored following administration of chlorambucil, as they may have an increased risk of seizures. As with any potentially epileptogenic drug, caution should be exercised when administering chlorambucil to patients with a history of seizure disorder, head trauma, or receiving other potentially epileptogenic drugs.
Renal
Patients with evidence of impaired renal function should be carefully monitored as they are prone to additional myelosuppression associated with azotemia.
Respiratory
Severe interstitial pulmonary fibrosis has been reported in patients with chronic lymphocytic leukemia on long-term chlorambucil therapy. Pulmonary fibrosis may be reversible on withdrawal of chlorambucil.
Sexual Function/Reproduction
Chlorambucil may cause suppression of ovarian function. Amenorrhea has been reported following chlorambucil therapy.
Azoospermia has been observed as a result of therapy with chlorambucil although it is estimated that a total dose of at least 400 mg is necessary.
Varying degrees of recovery of spermatogenesis have been reported in patients with lymphoma following treatment with chlorambucil in total doses of 410 to 2600 mg.
As with other cytotoxic agents LEUKERAN® is potentially teratogenic.
As with all cytotoxic chemotherapy, adequate contraceptive precautions should be advised when either partner is receiving chlorambucil.
Chlorambucil has been shown to cause chromatid or chromosome damage in man.
Skin
Rare instances of skin rash progressing to erythema multiforme, toxic epidermal necrolysis, or Stevens-Johnson syndrome have been reported. Chlorambucil should be discontinued promptly in patients who develop skin reactions.
7.1 Special Populations
7.1.1 Pregnant Women
The use of chlorambucil should be avoided whenever possible during pregnancy. However, when cytotoxic drugs are used in pregnancy, the possible teratogenic effect on the fetus should be kept in mind. It is therefore advisable to delay treatment with these drugs as long as possible and certainly until after the first three months of pregnancy. In any individual case, the potential hazard to the fetus must be balanced against the expected benefit to the mother.
7.1.2 Breast-feeding
Mothers receiving LEUKERAN® should not breast feed.
It is unknown if the drug is excreted in human milk. Because many drugs are excreted in human milk precaution should be exercised.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness in children have not been established.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No data is available.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
For this product there is no modern clinical documentation which can be used as support for determining the frequency of undesirable effects. Undesirable effects may vary in their incidence depending on the dose received and also when given in combination with other therapeutic agents.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The following convention has been utilised for the classification of frequency:
Very common: ≥1/10 (≥10%);
Common (frequent): ≥1/100 and <1/10 (≥1% and <10%);
Uncommon (infrequent): ≥1/1000 and <1/100 (≥0.1% and <1%);
Rare: ≥1/10,000 and <1/1000 (≥0.01 and <0.1);
Very rare: <1/10,000 (<0.01%);
Not known (cannot be estimated from the available data).
| Body System | Side Effects | |
|---|---|---|
| Neoplasms benign, malignant and unspecified (including cysts and polyps) | Common | Acute secondary hematologic malignancies (especially leukemia and myelodysplastic syndrome), particularly after long term treatment. |
| Blood and lymphatic system disorders | Very common | Leukopenia, neutropenia, thrombocytopenia, pancytopenia or bone marrow suppression1. |
| Common | Anaemia. | |
| Very rare | Irreversible bone marrow failure. | |
| Immune system disorders | Rare | Hypersensitivity such as urticaria and angioneurotic oedema following initial or subsequent dosing. (See Skin and subcutaneous tissue disorders) |
| Nervous system disorders | Common | Seizures in the paediatric population with nephrotic syndrome. |
| Rare | Convulsions 2, partial and/or generalised in the paediatric population and adults receiving therapeutic daily doses or high pulse dosing regimens of chlorambucil. | |
| Very rare | Movement disorders including tremor, muscle twitching and myoclonus in the absence of convulsions. Peripheral neuropathy. | |
| Respiratory, thoracic and mediastinal disorders | Very rare | Interstitial pulmonary fibrosis3, interstitial pneumonia. |
| Gastrointestinal disorders | Common | Gastro-intestinal disorders such as nausea and vomiting, diarrhoea and mouth ulceration. |
| Hepatobiliary disorders | Rare | Hepatoxicity, jaundice. |
| Skin and subcutaneous tissue disorders | Uncommon | Rash. |
| Rare | Stevens-Johnson syndrome, toxic epidermal necrolysis4. (See Immune system disorders) | |
| Renal and urinary disorders | Very rare | Sterile cystitis. |
Reproductive system and breast disorders | Not known | Amenorrhoea, azoospermia, infertility. |
| General disorders and administration site conditions | Rare | Pyrexia. |
- 1. Although bone marrow suppression frequently occurs, it is usually reversible if the chlorambucil is withdrawn early enough. However, irreversible bone marrow failure has been reported. (See Serious WARNINGS AND PRECAUTIONS)
- 2. Patients with a history of seizure disorder may be particularly susceptible (see WARNINGS AND PRECAUTIONS/Neurologic).
- 3. Severe interstitial pulmonary fibrosis has occasionally been reported in patients with chronic lymphocytic leukemia on long-term chlorambucil therapy. Pulmonary fibrosis may be reversible on withdrawal of chlorambucil. (see WARNINGS AND PRECAUTIONS/Respiratory)
- 4. Skin rash has been reported to progress to serious conditions including Stevens-Johnson syndrome and toxic epidermal necrolysis. (see WARNINGS AND PRECAUTIONS/Skin)
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions Box
9.2 Overview
Purine nucleoside analogues (such as fludarabine, pentostatin and cladribine) increased the cytotoxicity of chlorambucil ex vivo; however, the clinical significance of this finding is unknown.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
LEUKERAN® (chlorambucil) is an aromatic nitrogen mustard derivative which acts as a bifunctional alkylating agent. Alkylation takes place through the formation of a highly reactive ethylenimonium radical. A probable mode of action involves cross-linkage of the ethylenimonium derivative between two strands of helical DNA and subsequent interference with replication. In addition to interference with DNA replication, chlorambucil induces cellular apoptosis via the accumulation of cytosolic p53 and subsequent activation of an apoptosis promoter (Bax).
10.2 Pharmacodynamics
The cytotoxic effect of chlorambucil is due to both chlorambucil and its major metabolite, phenylacetic acid mustard (see Pharmacokinetics; Metabolism)
Mechanism of resistance
Chlorambucil is an aromatic nitrogen mustard derivative and resistance to nitrogen mustards has been reported to be secondary to: alterations in the transport of these agents and their metabolites via various multi-resistant proteins, alterations in the kinetics of the DNA
Serious Drug Interactions
Vaccinations with live organism vaccines are not recommended in immunocompromised individuals (see WARNINGS AND PRECAUTIONS/Immune).
Animal studies indicate that patients who receive phenylbutazone may require a reduction of the standard chlorambucil doses because of the possibility of enhanced chlorambucil toxicity.
cross-links formed by these agents and changes in apoptosis and altered DNA repair activity. Chlorambucil is not a substrate of multi-resistant protein 1 (MRP1 or ABCC1), but its glutathione conjugates are substrates of MRP1 (ABCC1) and MRP2 (ABCC2).
10.3 Pharmacokinetics
Absorption: Chlorambucil is well absorbed by passive diffusion from the gastrointestinal tract and is measurable within 15-30 minutes of administration. The bioavailability of oral chlorambucil is approximately 70 % to 100 % following administration of single doses of 10-200 mg. In a study of 12 patients administered approximately 0.2 mg/kg of oral chlorambucil, the mean dose adjusted maximum plasma concentration (492 ± 160 nanograms/ml) occurred between 0.25 and 2 hours after administration.
Consistent with the rapid, predictable absorption of chlorambucil, the inter-individual variability in the plasma pharmacokinetics of chlorambucil has been shown to be relatively small following oral dosages of between 15 and 70 mg (2-fold intra-patient variability, and a 2-4 fold interpatient variability in AUC).
The absorption of chlorambucil is reduced when taken after food. In a study of ten patients, food intake increased the median time to reach Cmax by greater than 100%, reduced the peak plasma concentration by greater than 50% and reduced mean AUC (0- ) by approximately 27% (see Dosage & Administration).
Distribution: Chlorambucil has a volume of distribution of approximately 0.14-0.24 L/kg. Chlorambucil covalently binds to plasma proteins, primarily to albumin (98%), and covalently binds to red blood cells.
Metabolism: Chlorambucil is extensively metabolised in the liver by monodichloroethylation and β-oxidation, forming phenylacetic acid mustard (PAAM) as the major metabolite, which possesses alkylating activity in animals. Chlorambucil and PAAM degrade in vivo forming monohydroxy and dihydroxy derivatives. In addition, chlorambucil reacts with glutathione to form mono- and diglutathionyl conjugates of chlorambucil.
Following the administration of approximately 0.2 mg/kg of oral chlorambucil, PAAM was detected in the plasma of some patients as early as 15 minutes and mean dose adjusted plasma concentration (Cmax) of 306 ± 73 nanograms/ml occurred within 1 to 3 hours.
Excretion: The terminal phase elimination half-life ranges from 1.3 - 1.5 hours for chlorambucil and is approximately 1.8 hours for PAAM. The extent of renal excretion of unchanged chlorambucil or PAAM is very low; less than 1 % of the administered dose of each of these is excreted in the urine in 24 hours, with the rest of the dose eliminated mainly as monohydroxy and dihydroxy derivatives.
Special Populations and Conditions
Geriatrics: No specific studies have been carried out in older people. However, monitoring of renal or hepatic function is advised. In the event of impairment, caution should be exercised (See DOSAGE AND ADMINISTRATION/Dosing Considerations).
Hepatic Insufficiency: Patients with hepatic impairment should be closely monitored for signs and symptoms of toxicity (See DOSAGE AND ADMINISTRATION/Dosing Considerations).
Renal Insufficiency: Dose adjustment is not considered necessary in renally impaired patients.
11 STORAGE, STABILITY AND DISPOSAL
LEUKERAN® (chlorambucil) 2 mg Tablets should be stored in a refrigerator, 2°C to 8°C.
12 SPECIAL HANDLING INSTRUCTIONS
Tablets should be returned to the manufacturer for destruction. Proper precautions should be taken in packaging those materials for transport.
All materials which have come in contact with cytotoxic drugs should be segregated and incinerated at 1000ºC or more. Sealed containers may explode.
Personnel regularly involved in the preparation and handling of cytotoxic agents should have bi-annual blood examinations.
Provided the outer coating is intact, there is no risk to handling. LEUKERAN® Tablets should not be divided.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Chlorambucil
Chemical name: Benzenebutanoic acid, 4-[bis(2-chloroethyl)amino]
Molecular formula and molecular mass: C14H19Cl2NO2 and 304.22 g/mol
Structural formula:
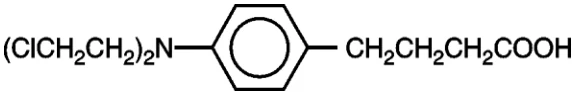
Physicochemical properties:
pKa: 5.8
Description: Flattened needles from petroleum ether. Melting point of 64-66°C. Soluble at 20°C in 1.5 parts alcohol, in 2.5 parts chloroform, in 2 parts acetone. Practically insoluble in water.
14 NON-CLINICAL TOXICOLOGY
Pharmacologic studies in rats showed that oral absorption is good, being slightly less than intraperitoneal absorption. A single dose of 12.5 mg/kg intraperitoneally produces typical nitrogen mustard effects. These include loss of weight the first three days, atrophy of intestinal mucosa and of lymphoid organs, severe lymphopenia becoming maximal in four days, transient mild anemia lasting ten days, and thrombocytopenia. Rapid recovery occurs, commonly within 72 hours, and the animal appears normal in about one week, although the bone marrow and blood may not become completely normal for about three weeks. An intraperitoneal dose of 18.5 mg/kg kills about 50% of the rats, with the development of convulsions. As much as 50 mg/kg has been given orally to rats as a single dose with recovery. Chlorambucil is only partially radiomimetic, producing chiefly the lymphoid effects of x-radiation as contrasted with MYLERAN (busulfan) which produces mainly the myeloid effects.
In human subjects, single oral doses of 20 mg or more may produce nausea and vomiting. In therapeutic doses, the depressant effect on the bone marrow is only moderate and rapidly reversible. Patients with lymphomas are more sensitive to the drug and smaller doses are indicated and are therapeutically useful. With excessive doses or prolonged therapy amounting to a total accumulated dosage approaching 6.5 mg/kg (about 450 mg per patient) patients may develop pancytopenia with possible irreversible bone marrow damage. Patients will usually respond to considerably less total dosage of drug than this if they are to respond at all.