


Product Monograph - Mar-Mycophenolic Acid
RECENT MAJOR LABEL CHANGES
None at the time of authorisation
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ...................................................................................................... 2
TABLE OF CONTENTS ........................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................................ 4
1 INDICATIONS ........................................................................................................................ 4
1.1 Pediatrics .............................................................................................................................. 4
1.2 Geriatrics .............................................................................................................................. 4
2 CONTRAINDICATIONS ........................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ....................................................................... 5
4 DOSAGE AND ADMINISTRATION ........................................................................................... 5
4.1 Dosing Considerations .......................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ..................................................................... 5
4.3 Reconstitution ...................................................................................................................... 6
4.4 Administration ...................................................................................................................... 6
4.5 Missed Dose ......................................................................................................................... 6
5 OVERDOSAGE ....................................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................................ 6
7 WARNINGS AND PRECAUTIONS ............................................................................................ 7
7.1 Special Populations ............................................................................................................. 10
7.1.1 Pregnant Women ............................................................................................................... 10
7.1.2 Breast-feeding .................................................................................................................... 10
7.1.3 Pediatrics ............................................................................................................................ 11
7.1.4 Geriatrics ............................................................................................................................ 11
8 ADVERSE REACTIONS .......................................................................................................... 11
8.1 Adverse Reaction Overview................................................................................................ 11
8.2 Clinical Trial Adverse Reactions .......................................................................................... 11
8.5 Post-Market Adverse Reactions ......................................................................................... 15
9 DRUG INTERACTIONS .......................................................................................................... 16
9.2 Drug Interactions Overview ................................................................................................ 16
9.4 Drug-Drug Interactions ....................................................................................................... 17
9.5 Drug-Food Interactions ....................................................................................................... 20
9.6 Drug-Herb Interactions ....................................................................................................... 20
9.7 Drug-Laboratory Test Interactions ..................................................................................... 20
10 CLINICAL PHARMACOLOGY ................................................................................................. 20
10.1 Mechanism of Action ......................................................................................................... 20
10.2 Pharmacodynamics ............................................................................................................ 21
10.3 Pharmacokinetics ............................................................................................................... 21
11 STORAGE, STABILITY AND DISPOSAL ................................................................................... 23
12 SPECIAL HANDLING INSTRUCTIONS ..................................................................................... 23
PART II: SCIENTIFIC INFORMATION ................................................................................................. 24
13 PHARMACEUTICAL INFORMATION ...................................................................................... 24
14 CLINICAL TRIALS ................................................................................................................. 25
14.1 Trial Design and Study Demographics ................................................................................ 25
14.2 Study Results ...................................................................................................................... 25
14.3 Comparative Bioavailability Studies ................................................................................... 27
15 MICROBIOLOGY .................................................................................................................. 29
16 NON-CLINICAL TOXICOLOGY ............................................................................................... 29
17 SUPPORTING PRODUCT MONOGRAPHS ............................................................................... 30
PATIENT MEDICATION INFORMATION ............................................................................................ 31
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
MAR-MYCOPHENOLIC ACID (mycophenolate sodium) is indicated for:
- the prophylaxis of organ rejection in patients receiving allogeneic renal transplants, administered in combination with cyclosporine, and corticosteroids.
1.1 Pediatrics
Safety and efficacy in pediatric patients have not been established. Limited pharmacokinetic data are available for pediatric renal transplant patients (see 10.3 Pharmacokinetics, Special Populations and Conditions, Pediatrics).
1.2 Geriatrics
Patients > 65 years may generally be at increased risk of adverse drug reactions due to an immunosuppression. Based on the controlled mycophenolic acid clinical trials, patients > 65 receiving mycophenolic acid as part of a combination immunosuppressive regimen, did not show an increased risk of adverse reactions, compared to younger patients.
No dose adjustment is required in this patient population.
2 CONTRAINDICATIONS
- MAR-MYCOPHENOLIC ACID (mycophenolate sodium) is contraindicated in patients with a hypersensitivity to mycophenolate sodium, mycophenolic acid, mycophenolate mofetil, or to any of its excipients (see 6 DOSAGE FORMS, STRENGTH, COMPOSITION AND PACKAGING).
- MAR-MYCOPHENOLIC ACID is contraindicated during pregnancy due to its mutagenic and teratogenic potential.
- MAR-MYCOPHENOLIC ACID is contraindicated in women of childbearing potential not using highly effective contraceptive methods (see 7.1.1 Pregnant Women).
- MAR-MYCOPHENOLIC ACID should not be initiated in women of childbearing potential without providing a pregnancy test result to rule out unintended use in pregnancy.
- MAR-MYCOPHENOLIC ACID is contraindicated in women who are breastfeeding.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- MAR-MYCOPHENOLIC ACID should be used in combination with cyclosporine and corticosteroid therapy.
- MAR-MYCOPHENOLIC ACID should be taken on an empty stomach, one hour before or two hours after food intake (see 9.5 Drug-Food Interactions).
4.2 Recommended Dose and Dosage Adjustment
- The recommended dose in adults is 720 mg (four 180 mg or two 360 mg tablets) administered twice daily (1.440 g total daily dose).
- Geriatric Use: No dose adjustments are required. The recommended dose is 720 mg administered twice daily.
- Pediatric Use: Safety and efficacy in pediatric patients have not been established. Limited pharmacokinetic data are available for pediatric renal transplant patients. (see 10.3 Pharmacokinetics Special Populations and Conditions, Pediatrics).
- Treatment during Rejection Episodes: Renal transplant rejection does not affect MPA pharmacokinetics; dosage reduction or interruption of MAR-MYCOPHENOLIC ACID is not required.
- Patients with Renal Impairment: No dose adjustments are needed in patients experiencing delayed post-operative renal graft function. Patients with severe chronic renal impairment (GFR < 25 mL/min1/1.73 m2) should be carefully monitored.
- Patients with Hepatic Impairment: No dose adjustments are needed for renal transplant patients with hepatic parenchymal disease.
- Patients Developing Neutropenia: If neutropenia develops (ANC < 1.3×10³ /µL), dosing with MAR-MYCOPHENOLIC ACID should be interrupted or the dose reduced, appropriate diagnostic tests performed, and the patient managed appropriately (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
Serious Warnings and Precautions
- Increased susceptibility to infection and the possible development of lymphoma and other neoplasms may result from immunosuppression. Only physicians experienced in immunosuppressive therapy and management of solid organ transplant patients should prescribe MAR-MYCOPHENOLIC ACID (mycophenolate sodium) Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physician responsible for maintenance therapy should have complete information requisite for the follow up of the patient.
- Female users of childbearing potential must use contraception. Use of MAR-MYCOPHENOLIC ACID during pregnancy is associated with increased risks of pregnancy loss and congenital malformations.
4.3 Reconstitution
Not Applicable
4.4 Administration
- Patients are to be instructed that MAR-MYCOPHENOLIC ACID tablets should not be crushed, chewed, or cut prior to ingesting but to be swallowed whole in order to maintain the integrity of the enteric coating.
4.5 Missed Dose
- Not applicable
5 OVERDOSAGE
There have been anecdotal reports of deliberate or accidental overdoses with mycophenolic acid, whereas not all patients experienced related adverse events.
In those overdose cases in which adverse events were reported, the events fall within the known safety profile of the class. Accordingly an overdose of MAR-MYCOPHENOLIC ACID could possibly result in over suppression of the immune system and may increase the susceptibility to infection including opportunistic infections, fatal infections and sepsis. If blood dyscrasias occur (e.g. neutropenia with absolute neutrophil count < 1.5 x 10³ / micro L or anaemia) it may be appropriate to interrupt or discontinue MAR-MYCOPHENOLIC ACID (see 7 WARNINGS AND PRECAUTIONS, Hematologic and 8.2 Clinical Trail Adverse Reactions).
Possible signs and symptoms of acute overdose could include the following: hematological abnormalities such as leukopenia and neutropenia, and gastrointestinal symptoms such as abdominal pain, diarrhea, nausea and vomiting, and dyspepsia. General supportive measures and symptomatic treatment should be followed in all cases of over dosage. Although dialysis may be used to remove the inactive metabolite MPAG, it would not be expected to remove clinically significant amounts of the active moiety MPA due to the 98% plasma protein binding of MPA. By interfering with enterohepatic circulation of MPA, activated charcoal or bile acid sequestrants, such as cholestyramine, may reduce the systemic MPA exposure.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764- 7669)
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| oral | Delayed release tablets/180 mg and 360 mg | Colloidal silicon dioxide, crospovidone, lactose monohydrate, magnesium stearate, povidone (K-30), and starch The enteric coating of the tablet consists of hypromellose phthalate, iron oxide yellow, and indigotine (180 mg tablets) or iron oxide red (360 mg tablets), and titanium dioxide. The non-volatile components of film coating and imprinting ink are ferrosoferric oxide, hypromellose, polyethylene glycol, propylene glycol, and shellac glaze. |
MAR-MYCOPHENOLIC ACID (mycophenolate sodium) delayed-release tablets are available in the following strengths which are equivalent to mycophenolic acid 180 mg and 360 mg:
180 mg: Lime green enteric coated round tablet with bevelled edges and imprinted with "HP 544" on one side and plain on other side, containing 180 mg mycophenolic acid as mycophenolate sodium. Provided in unit dose of 10 tablets/blister pack; 12 packs/carton.
360 mg: Pale orange-red, enteric coated ovaloid tablet imprinted with "HP 545" on one side and plain on other side, containing 360 mg mycophenolic acid as mycophenolate sodium. Provided in unit dose of 10 tablets/blister pack; 12 packs/carton.
7 WARNINGS AND PRECAUTIONS
General
Patients receiving MAR-MYCOPHENOLIC ACID should be instructed to immediately report any evidence of infection, unexpected bruising, bleeding, or any other manifestation of bone marrow suppression.
Patients should not donate blood during therapy or for at least 6 weeks following discontinuation of mycophenolate. Men should not donate semen during therapy or for 90 days following discontinuation of mycophenolate.
Carcinogenesis and Mutagenesis
Patients receiving immunosuppressive regimens involving combinations of drugs, including MAR-MYCOPHENOLIC ACID, as part of an immunosuppressive regimen are at an increased risk of developing lymphomas and other malignancies, particularly of the skin. The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. As general advice to minimize the risk for skin cancer, exposure to sunlight and UV light should be limited by wearing protective clothing and using a sunscreen with a high protection factor.
Endocrine and Metabolism
On theoretical grounds, because MAR-MYCOPHENOLIC ACID is an IMPDH Inhibitor, it should be avoided in patients with rare hereditary deficiency of hypoxanthine-guanine phosphoribosyl-transferase (HGPRT) such as Lesch- Nyhan and Kelley-Seegmiller syndrome.
Gastrointestinal
Because mycophenolic acid derivatives have been associated with an increased incidence of digestive system adverse events, including infrequent cases of gastrointestinal tract ulceration, hemorrhage, and perforation, MAR-MYCOPHENOLIC ACID should be administered with caution in patients with active serious digestive system disease. Gastrointestinal adverse events are common in patients receiving MPA treatment.
Gastrointestinal bleeding (requiring hospitalization), gastrointestinal tract ulceration, and perforation have rarely been reported in de novo renal transplant patients or maintenance patients treated with mycophenolic acid during clinical trials. Most patients receiving mycophenolic acid were also receiving other drugs known to be associated with these complications. Patients with active peptic ulcer disease were excluded from enrollment in studies with mycophenolic acid.
Hematologic
Cases of pure red cell aplasia (PRCA) have been reported in patients treated with mycophenolic acid or mycophenolate mofetil (MMF) in combination with other immunosuppressive agents (see 8.5 Post- Market Adverse Reactions). The mechanism for mycophenolic acid or MMF-induced PRCA is unknown; the relative contribution of other immunosuppressants and their combinations in an immunosuppressive regimen is also unknown. In some cases PRCA was found to be reversible with dose reduction or cessation of therapy with mycophenolic acid. In transplant patients, however, reduced immunosuppression may place the graft at risk. Changes to MAR-MYCOPHENOLIC ACID therapy should only be undertaken under appropriate supervision in transplant recipients in order to minimize the risk of graft rejection.
Patients receiving MAR-MYCOPHENOLIC ACID should be monitored for blood dyscrasias (e.g. neutropenia or anemia) (see 7 WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests). The development of neutropenia may be related to mycophenolic acid itself, concomitant medications, viral infections, or some combination of these events. If blood dyscrasias occur (e.g. neutropenia with absolute neutrophil count [ANC < 1.5×10³/µL] or anemia), dosing with MAR-MYCOPHENOLIC ACID should be interrupted or the dose reduced, appropriate diagnostic tests performed, and the patient managed appropriately (see 4.2 Recommended Dose and Dosage Adjustment).
Hepatic/Biliary/Pancreatic
In view of the significant reduction in the AUC of MPA by cholestyramine, caution should be used in the concomitant administration of MAR-MYCOPHENOLIC ACID with drugs that interfere with enterohepatic recirculation because of the potential to reduce the efficacy of MAR-MYCOPHENOLIC ACID.
Immune
Oversuppression of the immune system can also increase susceptibility to infection, including opportunistic infections, fatal infections, and sepsis.
Cases of progressive multifocal leukoencephalopathy (PML), sometimes fatal, have been reported in patients treated with mycophenolate sodium and mycophenolate mofetil (MMF) which both metabolize to the same active form of mycophenolic acid (MPA) in the body. Hemiparesis, apathy, confusion, cognitive deficiencies and ataxia were the most frequent clinical features observed. The reported cases generally had risk factors for PML, including treatment with immunosuppressants and impairment of immune functions. In immunosuppressed patients, physicians should consider PML in the differential diagnosis in patients reporting neurological symptoms and consultation with a neurologist should be considered as clinically indicated. Polyomavirus associated nephropathy (PVAN), especially due to BK virus infection (BK virus associated nephropathy [BKVAN]), should be included in the differential diagnosis in immunosuppressed patients with deteriorating renal function (see 8.5 Post- Market Adverse Reactions). Consideration should be given to reducing the amount of immunosuppression in patients who develop PML or PVAN. In transplant patients, physicians should also consider the risk that reduced immunosuppression represents to the graft.
PVAN and BKVAN are associated with serious outcomes, sometimes leading to renal graft loss (see 8.5 Post-Market Adverse Reactions). Patient monitoring may help detect patients at risk for polyomavirus or BK virus-associated nephropathy.
Reactivation of hepatitis B (HBV) or hepatitis C (HCV) have been reported in patients treated with immunosuppressants, including the mycophenolic acid (MPA) derivatives mycophenoate sodium and MMF. Monitoring infected patients for clinical and laboratory signs of active HBV or HCV infection is recommended.
Monitoring and Laboratory Tests
Complete blood count should be performed weekly during the first month, twice monthly for the second and the third month of treatment, then monthly through the first year. If neutropenia develops (ANC < 1.3x10³ /µL) dosing with MAR-MYCOPHENOLIC ACID should be interrupted or the dose reduced, appropriate tests performed, and the patient managed accordingly (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
Renal
Subjects with severe chronic renal impairment (GFR < 25 mL/min/1.73 m2) may present higher plasma MPAG AUCs relative to subjects with lesser degrees of renal impairment or normal healthy volunteers. No data are available on the safety of long-term exposure to these levels of MPAG.
In the de novo study, 18.3% of mycophenolic acid patients versus 16.7% in the MMF group experienced delayed graft function (DGF). Patients with DGF experienced a higher incidence of certain adverse events such as anemia, leukopenia, and hyperkalemia than patients without DGF, but these events in DGF patients were not more frequent in patients receiving mycophenolic acid than MMF. No dose adjustment is recommended for these patients; however, such patients should be carefully observed (see 4.2 Recommended Dose and Dose Adjustment).
Reproductive Health: Female and Male Potential
Fertility
Mycophenolate sodium had no effect on fertility of male rats at oral doses up to 40 mg/kg/day. The systemic exposure at this dose represents approximately 9 times the clinical exposure at the tested clinical dose of 1.44 g/day mycophenolate sodium. No effects on female fertility were seen up to a dose of 20 mg/kg/day, a dose at which maternal toxicity and embryotoxicity were already observed and yielding an exposure similar to that observed at the maximum recommended clinical dose.
Contraception
Before the start of treatment, female and male patients of reproductive potential must be made aware of the increased risk of pregnancy loss and congenital malformations and must be counseled regarding pregnancy prevention, and planning. Women of child bearing potential should use two reliable forms of contraception simultaneously, including at least one highly effective method, before beginning MAR-MYCOPHENOLIC ACID therapy, during therapy, and for six weeks following discontinuation of therapy, unless abstinence is the chosen method of contraception.
Prior to starting therapy with MAR-MYCOPHENOLIC ACID, female patients of childbearing potential must have two negative serum or urine pregnancy tests with a sensitivity of at least 25 mIU/mL; the second test, if feasible, should be performed 8-10 days after the first one and immediately before starting MAR-MYCOPHENOLIC ACID. Repeat pregnancy tests should be performed during routine follow-up visits. Results of all pregnancy tests should be discussed with the patient. Patients should be instructed to consult their physician immediately should pregnancy occur.
Sexually active men are recommended to use condoms during treatment and for at least 90 days after cessation of treatment. Condom use applies for both reproductively competent and vasectomized men, because the risks associated with the transfer of seminal fluid also apply to men who have had a vasectomy. In addition, female partners of male patients are recommended to use highly effective contraception during treatment and for total of 90 days after the last dose of MAR-MYCOPHENOLIC ACID (see 9.4 Drug-Drug Interactions). If pregnancy does occur during treatment, the physician and patient should discuss the desirability of continuing the pregnancy.
Sensitivity/Resistance
Vaccinations: During treatment with MAR-MYCOPHENOLIC ACID, Patients should be advised that during treatment with MPA, vaccinations may be less effective and the use of live attenuated vaccines should be avoided.
Influenza vaccination may be of value. Prescribers should refer to National Guidelines for influenza vaccination.
7.1 Special Populations
7.1.1 Pregnant Women
MAR-MYCOPHENOLIC ACID is contraindicated during pregnancy and in women of childbearing potential not using highly effective contraceptive methods. MAR-MYCOPHENOLIC ACID should not be initiated in women of childbearing potential without providing a pregnancy test result to rule out unintended use in pregnancy (see 2 CONTRAINDICATIONS and 8.5 Post Market Adverse Reactions). MAR-MYCOPHENOLIC ACID is a powerful teratogen and mutagen. Spontaneous abortion (rate of 45-49% compared to a reported rate between 12 and 33% in solid organ transplant patients treated with other immunosuppressants) and congenital malformations (estimated rate of 23-27%) have been reported following mycophenolate mofetil (MMF) exposure during pregnancy. For comparison the risk of malformations is estimated at approximately 2% of live births in the overall population and at approximately 4 to 5 % in solid organ transplant patients treated with immunosupressants other than mycophenolate mofetil (see 8.5 Post Market Adverse Reactions).
Studies in animals have shown reproductive toxicity (see 16 NON-CLINICAL TOXICOLOGY: Reproductive and Developmental Toxicity).
7.1.2 Breast-feeding
MAR-MYCOPHENOLIC ACID is contraindicated during breastfeeding due to the potential for serious adverse reactions in nursing infants (see 2 CONTRAINDICATIONS). Studies in rats have shown mycophenolate mofetil is excreted in milk. It is not known whether this drug is excreted in human milk.
7.1.3 Pediatrics
See 1.1 Pediatrics.
7.1.4 Geriatrics
See 1.2 Geriatrics.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common (>25%) adverse events from clinical trial data from de novo kidney transplant patients treated with mycophenolic acid include constipation, nausea, and urinary tract infection. Clinical trial data from maintenance patients treated with mycophenolic acid show that nausea, diarrhea and nasopharyngitis were the most frequently observed adverse reactions (> 15%). Fatal infections were rarely observed in patients receiving mycophenolic acid (0.5%) in controlled clinical trials.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse events reported in > 10% of patients receiving mycophenolic acid or MMF in the 12-months de novo renal study and maintenance renal study, when used in combination with cyclosporine are listed in Table 2. Adverse event rates were similar between mycophenolic acid and MMF in both de novo and maintenance patients.
Table 2: Adverse Events (%) in Controlled de novo and Maintenance Renal Studies Reported in > 10% of Patients
| de novo Renal Study | Maintenance Renal Study | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
mycophenolic acid 1.44 g/day (n=213) | MMF 2 g/day (n=210) | mycophenolic acid 1.44 g/day (n=159) | MMF 2 g/day (n=163) | |||||||||||
| Blood and lymphatic system disorders | ||||||||||||||
| Anemia | 21.6 | 21.9 | - | - | ||||||||||
| Leukopenia | 19.2 | 20.5 | - | - | ||||||||||
| Gastrointestinal system disorders | ||||||||||||||
| Constipation | 38 | 39.5 | - | - | ||||||||||
| Nausea | 29.1 | 27.1 | 24.5 | 19 | ||||||||||
| Diarrhea | 23.5 | 24.8 | 21.4 | 24.5 | ||||||||||
| Vomiting | 23 | 20 | 15.1 | 12.9 | ||||||||||
| Dyspepsia | 22.5 | 19 | 13.8 | 14.7 | ||||||||||
| Upper abdominal pain | 14.1 | 14.3 | - | - | ||||||||||
| General and administrative site disorders | ||||||||||||||
| Edema | 16.9 | 17.6 | - | - | ||||||||||
| Edema lower limb | 15.5 | 17.1 | - | - | ||||||||||
| Edema peripheral | - | - | 10.7 | 12.3 | ||||||||||
| Pyrexia | 12.7 | 18.6 | - | - | ||||||||||
| Pain | 13.6 | 8.6 | - | - | ||||||||||
| Infections and infestations | ||||||||||||||
| Urinary tract infection | 29.1 | 33.3 | 10.1 | 11.7 | ||||||||||
| CMV infection | 20.2 | 18.1 | ||||||||||||
| Nasopharyngitis | - | - | 16.4 | 19.6 | ||||||||||
| Upper respiratory tract infection | - | - | 12.6 | 9.8 | ||||||||||
| Investigations | ||||||||||||||
| Increased blood creatinine | 14.6 | 10 | - | - | ||||||||||
| Metabolism and nutrition disorder | ||||||||||||||
| Hypocalcemia | 11.3 | 15.2 | - | - | ||||||||||
| Hyperuricemia | 12.7 | 13.3 | - | - | ||||||||||
| Hyperlipidemia | 12.2 | 9.5 | - | - | ||||||||||
| Hypokalemia | 12.7 | 9 | - | - | ||||||||||
| Hypophosphatemia | 10.8 | 8.6 | - | - | ||||||||||
| Musculoskeletal, connective tissue and bone disorder | ||||||||||||||
| Back pain | 11.7 | 6.2 | - | - | ||||||||||
| Arthralgia | - | - | 13.8 | 9.8 | ||||||||||
| Nervous system disorder | ||||||||||||||
| Insomnia | 23.5 | 23.8 | - | - | ||||||||||
| Tremor | 11.7 | 14.3 | - | - | ||||||||||
| Headache | 13.1 | 11 | 17.6 | 16.6 | ||||||||||
| Respiratory, thoracic and mediastinal disorder | ||||||||||||||
| Cough | - | - | 11.3 | 8 | ||||||||||
| Surgical and medical procedure | ||||||||||||||
| Post-operative pain | 23.9 | 18.6 | - | - | ||||||||||
| Vascular disorder | ||||||||||||||
| Hypertension | 18.3 | 18.1 | - | - | ||||||||||
Table 3 summarizes the incidence of opportunistic infections in de novo and maintenance transplant patients, which were similar in both treatment groups.
Table 3: Viral and Fungal Infections (%) Reported Over 0-12 Months
| de novo Renal Study | Maintenance Renal Study | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
mycophenolic acid 1.44 g/day (n = 213) | MMF 2 g/day (n = 210) | mycophenoli c acid 1.44 g/day (n = 159) | MMF 2 g/day (n = 163) | |||||||||
| (%) | (%) | (%) | (%) | |||||||||
| Any cytomegalovirus | 21.6 | 20.5 | 1.9 | 1.8 | ||||||||
| 4.7 | 4.3 | 0 | 0.6 | ||||||||
| Herpes simplex | 8 | 6.2 | 1.3 | 2.5 | ||||||||
| Herpes zoster | 4.7 | 3.8 | 1.9 | 3.1 | ||||||||
| Any fungal infection | 10.8 | 11.9 | 2.5 | 1.8 | ||||||||
| 5.6 | 6.2 | 0 | 1.8 | ||||||||
| 2.3 | 3.8 | 0.6 | 0 | ||||||||
Long term administration of mycophenolic acid (up to 30 months of exposure) did not show any unexpected changes in the pattern of adverse events including infections and malignancies.
The following adverse events were reported between 3% to <10% incidence in de novo and maintenance patients treated with mycophenolic acid in combination with cyclosporine and corticosteroids are listed in Table 4.
Table 4: Adverse Events Reported in 3% to <10% of Patients Treated with Mycophenolic Acid in Combination with Cyclosporine and Corticosteroids
de novo Renal Study | Maintenance Renal Study | |
|---|---|---|
| Blood and lymphatic disorders | Lymphocele, thrombocytopenia | Leukopenia, anemia |
| Cardiac disorder | Tachycardia | - |
| Eye disorder | Vision blurred | - |
| Endocrine disorders | Cushingoid, hirsutism | - |
| Gastrointestinal disorder | Flatulence, abdominal distension, sore throat, abdominal pain lower, abdominal pain, gingival hyperplasia, loose stool | Abdominal pain, constipation, gastroesophageal reflux disease, loose stool, flatulence, abdominal pain upper |
General disorders and administration site conditions | Fatigue, edema peripheral, chest pain | Fatigue, pyrexia, edema, chest pain |
| Infections and infestations | Nasopharyngitis, herpes simplex, upper respiratory tract infection, oral candidiasis, herpes zoster, sinusitis, wound infection, implant infection, pneumonia | Influenza, sinusitis |
Injury, poisoning, and procedural complications | Drug toxicity | Post procedural pain |
| Investigations | Hemoglobin decrease, blood pressure increased, liver function tests abnormal | Blood creatinine increase, weight increase |
| Metabolism and nutrition disorders | Hypercholesterolemia, hyperkalemia, hypomagnesemia, diabetes mellitus, hyperphosphatemia, dehydration, fluid overload, hyperglycemia, hypercalcemia | Dehydration, hypokalemia, hypercholesterolemia |
| Musculoskeletal and connective tissue disorders | Arthralgia, pain in limb, muscle cramps, myalgia | Pain in limb, back pain, muscle cramps, peripheral swelling, myalgia |
| Nervous system disorders | Dizziness (excluding vertigo) | Dizziness |
| Psychiatric disorders | Anxiety | Insomnia, depression |
| Renal and urinary disorders | Renal tubular necrosis, renal impairment, dysuria, hematuria, hydronephrosis, bladder spasm, urinary retention | - |
Respiratory, thoracic and mediastinal disorders | Cough, dyspnea, dyspnea exertional | Dyspnea, pharyngolaryngeal pain, sinus congestion |
Skin and subcutaneous tissue disorder | Acne, pruritus | Rash, contusion |
| Surgical and medical procedures | Complications of transplant surgery, post operative complications, post operative wound complication | - |
| Vascular disorder | Hypertension aggravated, hypotension | Hypertension |
The following opportunistic infections occurred rarely in the above controlled trials: aspergillus and cryptococcus.
The incidence of malignancies and lymphoma is consistent with that reported in the literature for this patient population. Lymphoma developed in 2 de novo patients (0.9%), (one diagnosed 9 days after treatment initiation) and in 2 maintenance patients (1.3%) (one was AIDS-related), receiving mycophenolic acid with other immunosuppressive agents in the 12-month controlled clinical trials. Non-melanoma skin carcinoma occurred in 0.9% de novo and 1.8% maintenance patients. Other types of malignancy occurred in 0.5% de novo and 0.6% maintenance patients.
Adverse Events Associated with MPA
The following adverse reactions have been associated with MPA (including MMF):
Gastrointestinal: colitis (sometimes caused by CMV), pancreatitis, esophagitis, intestinal perforation, gastrointestinal hemorrhage, gastric ulcers, duodenal ulcers, and ileus.
Respiratory: although not reported with mycophenolate sodium, interstitial lung disorders, including fatal pulmonary fibrosis, have been reported rarely with MPA administered as MMF and should be considered in the differential diagnosis of pulmonary symptoms ranging from dyspnea to respiratory failure in post transplant patients receiving MPA derivatives.
Infections and Infestation: Cases of progressive multifocal leukoencephalopathy (PML), sometimes fatal, have been reported in patients treated with mycophenolate sodium (mycophenolic acid) and mycophenolate mofetil (MMF). (see 7 WARNINGS AND PRECAUTIONS, Immune).
Polyomavirus associated nephropathy (PVAN), especially due to BK virus infection is attributed to mycophenolic acid compounds (including mycophenolic acid) as a class effect (see 7 WARNINGS AND PRECAUTIONS, Immune).
Blood and Lymphatic system disorders: Agranulocytosis, neutropenia, pancytopenia. Cases of pure red cell aplasia (PRCA) have been reported in patients treated with mycophenolic acid compounds (including mycophenolic acid enteric-coated tablets) in combination with other immunosuppressive agents (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
8.5 Post-Market Adverse Reactions
The post marketing data of pregnant women exposed to mycophenolate mofetil (MMF) indicate that use of MPA during pregnancy is associated with an increased risk of congenital disorders and first trimester pregnancy loss.
Congenital Disorders:
Congenital malformations, including multiple malformations, have been reported postmarketing, in children of patients exposed to MPA in combination with other immunosuppressants during pregnancy.
The following malformations were most frequently reported:
- Facial malformations such as cleft lip, cleft palate, micrognathia and hypertelorism of the orbits;
Abnormalities of the ear (e.g. abnormally formed or absent external/middle ear) and eye (e.g.
- coloboma, microphthalmos);
- Malformations of the fingers (e.g. polydactyly, syndactyly, brachydactyly);
- Cardiac abnormalities such as atrial and ventricular septal defects;
- Oesophageal malformations (e.g. oesophageal atresia);
- Nervous system malformations (such as spina bifida)
In the medical literature, malformations in children from MPA exposed pregnancies have been reported in 23 to 27% of live births. For comparison the risk of malformations is estimated at approximately 2% of live births in the overall population and at approximately 4 to 5 % in solid organ transplant patients treated with immunosuppressants other than mycophenolate.
Pregnancy, Puerperium and Perinatal Conditions:
Cases of spontaneous abortions have been reported in patients exposed to MPA, mainly in the first trimester. In the medical literature, the risk has been reported at 45 to 49% following MPA exposure compared to a reported rate between 12 and 33% in solid organ transplant patients treated with other immunosuppressants.
Skin and subcutaneous tissue disorders:
Rash has been identified as an adverse drug reaction from post-approval clinical trials, post-marketing surveillance and spontaneous reports.
General disorders and administration site conditions: de novo purine synthesis inhibitors-associated acute inflammatory syndrome
Immune System Disorders:
Hypersensitivity reactions (including anaphylaxis)
Hypogammaglobulinemia:
There have been reports of hypogammaglobulinemia in adult patients treated with mycophenolate mofetil or mycophenolic acid in combination with other immunosuppressants. Consideration should be given, in patients developing recurrent infections, to have their serum immunoglobulins measured and monitored as needed.
Musculoskeletal and connective tissue disorders: asthenia
Respiratory Disorders:
Bronchiectasis:
In transplant patients treated with mycophenolic acid in combination with other immunosuppressants, cases of bronchiectasis have been reported. Considerations should be given, in patients developing persistent pulmonary symptoms such as cough, dyspnea or recurring respiratory infections, to investigate further to determine definitely if they present bronchiectasis.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Mycophenolic acid has been administered in combination with the following agents in clinical trials: antilymphocyte/thymocyte immunoglobulin, Simulect® (basiliximab), daclizumab, muromonab, cyclosporine, Prograf* (tacrolimus) and corticosteroids. The efficacy and safety of the use of mycophenolic acid enteric-coated tablets with other immunosuppressive agents have not been studied.
9.4 Drug-Drug Interactions
Table 5: Established or Potential Drug-Drug Interactions
| Drug | Reference | Effect | Clinical Comment |
|---|---|---|---|
| Antacids/ Antacids with magnesium and aluminium hydroxides | Single-dose of mycophenolic acid administered to 12 stable renal transplant patients alone and in combination with Maalox* (30 mL). | Absorption of a single dose of mycophenolic acid was decreased when administered in combination with Maalox* (30 mL). The Cmax and AUC(0-T) for MPA were 25% and 37% lower, respectively, than when mycophenolic acid was given alone. | Magnesium-aluminum containing antacids may be used intermittently (several doses/week) for the treatment of occasional dyspepsia. However, the chronic daily use of magnesium-aluminum containing antacids with MAR-MYCOPHENOLIC ACID is not recommended due to the potential for |
| Drug | Reference | Effect | Clinical Comment |
|---|---|---|---|
| decreased MPA exposure. | |||
Antibiotics eliminating β- glucuronidase- producing bacteria in the intestine (e.g. aminoglycoside, cephalosporin, fluoroquinolone, and penicillin classes of antibiotics) | Cellcept* | These types of antibiotics are postulated to interfere with MPAG/MPA enterohepatic recirculation thus leading to reduced systemic MPA exposure | Clinical relevance is unclear |
| Cyclosporine | Stable renal transplant patients. | Cyclosporine pharmacokinetics were unaffected by steady- state dosing of mycophenolic acid. | -- |
| Acyclovir | CellCept* Prescribing Information. | Higher plasma concentrations of both MPAG (mycophenolic acid glucuronide) and Acyclovir may occur in the presence of renal impairment. | The potential exists for these two drugs to compete for tubular secretion, resulting in a further increase in the concentration of both MPAG and Acyclovir. In this situation patients should be carefully followed up. |
| Gancyclovir | CellCept* Prescribing Information. | MPA and MPAG pharmacokinetics are unaffected by the addition of Gancyclovir. The clearance of Gancyclovir is unchanged in the setting of therapeutic MPA exposure. | In patients with renal impairment in which MAR-MYCOPHENOLIC ACID and Gancyclovir are coadministered the dose recommendations for Gancyclovir should be observed and patients monitored carefully. |
| Drug | Reference | Effect | Clinical Comment |
|---|---|---|---|
| Tacrolimus/ Neoral® | Calcineurin cross-over study in stable renal transplant patients | Mean MPA AUC was 19% higher and Cmax approximately 20% lower. Mean MPAG AUC and Cmax were approximately 30% lower on tacrolimus treatment compared to Neoral® treatment | -- |
Azathioprine/ mycophenolate mofetil | CellCept* Prescribing Information. | Inhibition of purine metabolism. | Given that azathioprine and mycophenolate mofetil inhibit purine metabolism, it is recommended that MAR-MYCOPHENOLIC ACID not be administered concomitantly with azathioprine or mycophenolate mofetil. |
| Cholestyramine and drugs that bind bile acids | CellCept* Prescribing Information. | Concomitant administration of cholestyramine leads to a reduction in the AUC of MPA. | Caution should be used when co- administering drugs or therapies that may bind bile acids, for example bile acid sequestrates or oral activated charcoal, because of the potential to reduce the efficacy of MAR-MYCOPHENOLIC ACID. |
| Oral contraceptives | CellCept* Prescribing Information. | None | Although not measured in a clinical trial, given the different metabolism of mycophenolic acid and oral contraceptives, no drug interaction between these two classes of drug is expected, however, given that the long term effect of MAR-MYCOPHENOLIC |
| ACID dosing on | |||
| Drug | Reference | Effect | Clinical Comment |
| the pharmacokinetics of oral contraceptives is not known, it is possible that the efficacy of oral contraceptives may be adversely affected | |||
| Proton Pump inhibitors | Clincal Expert report | In healthy volunteers, no changes in the pharmacokinetics of MPA were observed following concomitant administration of mycophenolic acid and pantoprazole | |
*All trademarks and registered trademarks are the property of their respective owners. SIMULECT and NEORAL are registered trademarks
9.5 Drug-Food Interactions
Compared to the fasting state, administration of mycophenolic acid 720mg with a high fat meal (55g fat, 1000 calories) had no effect on the systemic exposure (AUC) of MPA. However, there was a 33% decrease in the maximal concentration (Cmax) of MPA, significant delays in absorption of MPA (Tmax delayed up to 20 hours) were observed. To avoid variations in MPA absorption between doses, MAR-MYCOPHENOLIC ACID should be taken on an empty stomach (see 4.1 Dosing Considerations).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
MAR-MYCOPHENOLIC ACID (mycophenolate sodium), deliver the active moiety, mycophenolic acid (MPA). MPA is a potent, selective, uncompetitive, and reversible inhibitor of inosine monophosphate dehydrogenase (IMPDH), and therefore inhibits the de novo pathway of guanosine nucleotide synthesis without incorporation to DNA. Because T- and B-lymphocytes are critically dependent for their proliferation on de novo synthesis of purines, whereas other cell types can utilize salvage pathways, MPA has a potent cytostatic effect on lymphocytes. Thus the mode of action is complementary to calcineurin inhibitors which interfere with cytokine transcription and resting T-lymphocytes.
Mycophenolate sodium has been shown to prevent the occurrence of acute rejection in models of kidney allotransplantation, of heart allotransplantation and of heart xenotransplantation associated or not with other immunosuppressive treatment. Mycophenolate sodium also inhibited proliferative arteriopathy in experimental models of aortic allografts in rats as well as antibody production in mice.
10.2 Pharmacodynamics
Not available at the time of authorization
10.3 Pharmacokinetics
Table 6: Mean (±SD) Pharmacokinetic Parameters for MPA following Oral Administration of Mycophenolic acid to Renal Transplant Patients on Cyclosporine Based Immunosuppression
Study Patient | Mycophenolic acid enteric-coated tablets Dosing | N | Dose (mg) | Tmax* (hr) | Cmax (ug/ml) | AUC 0-12hr (ug*hr/ml) |
|---|---|---|---|---|---|---|
| Adult | Single | 24 | 720 | 2(0.8 - 8) | 26.1±12.0 | 66.5 ±22.6** |
| Pediatric*** | Single | 10 | 450/m2 | 2.5(1.5 - 24) | 36.3± 20.9 | 74.3± 22.5** |
| Adult | Multiple x 6 days, BID | 10 | 720 | 2(1.5 - 3.0) | 37.0 ±13.3 | 67.9± 20.3 |
| Adult | Multiple x 28 days, BID | 36 | 720 | 2.5(1.5 - 8) | 31.2± 18.1 | 71.2 ±26.3 |
| Adult | Chronic, Multiple dose, BID | |||||
| 2 weeks post-transplant | 12 | 720 | 1.8(1.0 - 5.3) | 15.0 ±10.7 | 28.6 ±11.5 | |
| 3 months post-transplant | 12 | 720 | 2(0.5 - 2.5) | 26.2 ±12.7 | 52.3 ±17.4 | |
| 6 months post-transplant | 12 | 720 | 2(0 - 3) | 24.1± 9.6 | 57.2± 15.3 | |
| Adult | Chronic, Multiple dose, BID | 18 | 720 | 1.5(0 - 6) | 18.9 ±7.9 | 57.4± 15.0 |
* median (range), ** AUC0-8, *** age range of 5 - 16 years
The mean pharmacokinetic parameters for MPA following the administration of mycophenolic acid in renal transplant patients on cyclosporine based immunosuppression are shown in Table 6. Single dose mycophenolic acid pharmacokinetics predict multiple dose pharmacokinetics. However, in the early post transplant period, mean MPA AUC and Cmax were approximately one-half of those measured six months post transplant.
After near equimolar dosing of Mycophenolate sodium (720 mg BID) and MMF (1000 mg BID) in both the single and multiple dose cross-over trials, mean systemic MPA exposure was similar.
Absorption
In vitro studies demonstrated that the mycophenolic acid does not release MPA under acidic conditions (pH < 5) as in the stomach but is highly soluble in neutral pH conditions as in the intestine. Following mycophenolic acid oral administration without food, consistent with its enteric-coated formulation, the median time to maximum concentration (Tmax) of MPA was 1.5 - 2.5 hours (range: 1.5 to 8 hours) compared to 1 hour (range: 0.5 to 3 hours) for mycophenolate mofetil (MMF). In stable renal transplant patients on cyclosporine based immunosuppression, gastrointestinal absorption of MPA was 93% and absolute bioavailability 71%. mycophenolic acid pharmacokinetics is dose proportional over the dose range of 180 to 2160 mg.
Food effect: Compared to the fasting state, administration of mycophenolic acid 720mg with a high fat meal (55g fat, 1000 calories) had no effect on the systemic exposure (AUC) of MPA. However, there was a 33% decrease in the maximal concentration (Cmax) of MPA, significant delays in absorption of MPA (Tmax delayed up to 20 hours) were observed. To avoid variations in MPA absorption between doses, mycophenolic acid should be taken on an empty stomach (see 4.1 Dosing Considerations).
Distribution: The volume of distribution at steady-state for MPA is 54.3 (± 25.2) L . MPA is highly protein bound to albumin, >98%. The protein binding of mycophenolic acid glucuronide (MPAG) is 82%. The free MPA concentration may increase under conditions of decreased protein binding (uremia, hepatic failure, and hypoalbuminemia). This may put patients at an increased risk of MPA-related adverse events.
Metabolism:
The half-life of MPA is 11.7 (± 3.2) hours and the clearance is 8.4 (± 1.8) L/hr. MPA is metabolized principally by glucuronyl transferase to the phenolic glucuronide of MPA, mycophenolic acid glucuronide (MPAG). MPAG is the predominant metabolite of MPA and does not manifest pharmacological activity. In stable renal transplant patients on cyclosporine based immunosuppression, approximately 28% of the oral mycophenolic acid dose is converted to MPAG by pre- systemic metabolism. The half-life of MPAG is longer than MPA, approximately 15.7 (± 3.9) hours and its clearance is 0.45 (± 0.15) L/hr.
Elimination
The majority of MPA (>60% of the dose) is eliminated in the urine primarily as MPAG and <3% as MPA. MPAG secreted in the bile is available for deconjugation by gut flora. The MPA resulting from this deconjugation may then be reabsorbed. Approximately 6-8 hours after mycophenolic acid enteric-coated tablets dosing, a second peak of MPA concentration can be measured which is consistent with reabsorption of the deconjugated MPA.
Special Populations and Conditions
- Pediatrics: Safety and efficacy in children have not been established. Limited pharmacokinetics data are available on the use of mycophenolic acid in children. Limited data are available at a dose of 450 mg/m2 body surface area in children. The mean MPA pharmacokinetic parameters for stable pediatric renal transplant patients, 5-16 years, on cyclosporine are shown in Table 6. At the same dose administered based on body surface area, the respective mean Cmax and AUC of MPA determined in children were higher by 33% and 18% than those determined for adults. The clinical impact of the increase in MPA exposure is not known.
- Geriatrics: Pharmacokinetics in the elderly have not been formally studied.
- Sex: There are no significant gender differences in mycophenolic acid pharmacokinetics.
- Ethnic Origin Following a single dose administration of 720 mg mycophenolic acid to 18 Japanese and Caucasian healthy subjects, the exposure (AUCinf) for MPA and MPAG were 15 and 22% lower in Japanese subjects compared to Caucasians. The peak concentrations (Cmax) for MPAG were similar between the two populations, however, Japanese subjects had 9.6% higher Cmax for MPA. These results do not suggest any clinically relevant differences.
- Hepatic Insufficiency In a single dose (1g MMF) study of 18 volunteers with alcoholic cirrhosis and 6 healthy volunteers, hepatic MPA glucuronidation processes appeared to be relatively unaffected by hepatic parenchymal disease when the pharmacokinetic parameters of healthy volunteers and alcoholic cirrhosis patients within this study were compared. However, it should be noted that for unexplained reasons, the healthy volunteers in this study had about a 50% lower AUC compared to healthy volunteers in other studies, thus making comparison between volunteers with alcoholic cirrhosis and health volunteers difficult. Effects of hepatic disease on this process probably depend on the particular disease. Hepatic disease with other etiologies may show a different effect.
Renal Insufficiency No specific pharmacokinetic studies in individuals with renal impairment were conducted with mycophenolic acid. MPA pharmacokinetic was unchanged over the range of normal to severely impaired renal function based on studies with mycophenolate mofetil. In contrast, MPAG exposure increased with decreased renal function; MPAG exposure being approximately 8 fold higher in the setting of anuria. Although dialysis may be used to remove the inactive metabolite MPAG, it
- would not be expected to remove clinically significant amounts of the active moiety MPA. This is in large part due to the high plasma protein binding of MPA.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15°C - 30°C. Protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
Tablets should not be crushed or cut.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
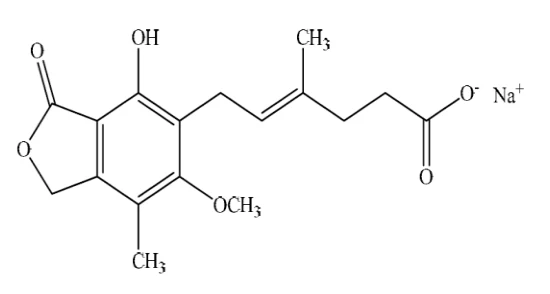
Proper name: mycophenolate sodium
Chemical name: Sodium (E)-6-(4-hydroxy-6-methoxy-7-methyl-3-oxo-1,3 dihydroisobenzofuran-5-yl)-4-methylhex-4-enoate
OR
4-Hexenoic acid, 6-(1,3-dihydro-4-hydroxy-6-methoxy- 7-methyl-3 oxo-5-isobenzofuranyl)-4-methylmonosodium salt, (E)-;
Molecular formula and molecular mass: C17H19O6 Na; 342.32 g/mol
Structural formula:
Physicochemical properties:
Physical Form: White or almost white, crystalline powder
Solubility: Slightly soluble in Water and in anhydrous Ethanol, very slightly soluble in Heptane.
The approximate solubility of Mycophenolate Sodium in various solvents is as under:
| Solvent | Solubility (mg/ml) at 25°C | Solubility Terms |
|---|---|---|
| Water | 1.008 | Slightly soluble |
| Anhydrous ethanol | 1.005 | Slightly soluble |
| Heptane | 0.101 | Very slightly soluble |
| Methanol | 80 | Soluble |
| Chloroform | 0.040 | Practically insoluble |
| Ethyl acetate | 0.037 | Practically insoluble |
| Di-isopropyl ether | 0.007 | Practically insoluble |
Solubility of Mycophenolate sodium in aqueous media at different pH is as under.
| pH of aqueous solution | Solubility at 25°C |
|---|---|
| 1.5 | 2.6 mg/ml |
| 3.0 | 6.0 mg/ml |
| 4.6 | 11.2 mg/ml |
| 6.8 | 82.5 mg/ml |
| 8.0 | 97.9 mg/ml |
Melting point range: 183 ºC – 190ºC.
Isomerism: Trans isomeric form. When exposed to actinic light for a longer duration, formation of Z isomer is observed.
Chirality: Not present
Polymorphism: Crystalline M2 Form
pKa: 8.32 and 8.14
Hygroscopicity: Non hygroscopic
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The safety and efficacy of mycophenolic acid (mycophenolate sodium) in combination with cyclosporine and corticosteroids for the prevention of organ rejection was assessed in two multicenter, randomized, double-blind trials in de novo and maintenance renal transplant patients compared to MMF.
14.2 Study Results
The de novo study was conducted in 423 renal transplant patients (ages 18-75 years) with the objective to confirm that mycophenolic acid and MMF were therapeutically equivalent.
Patients were administered either mycophenolic acid 1.44 g/day or MMF 2 g/day within 48 hours post- transplant for 12 months in combination with cyclosporine and corticosteroids. In the mycophenolic acid and MMF groups, 39.4% and 42.9% respectively, received antibody therapy as an induction treatment. The primary efficacy endpoint was the incidence of biopsy-proven acute rejection, graft loss, death or loss to follow-up at 6 months. The incidence of biopsy-proven acute rejection, graft loss, death or loss to follow-up was similar in mycophenolic acid and MMF-treated patients at 6 months, and met criteria confirming therapeutic equivalence, with similar results seen at 12 months (Table 7).
Table 7: Efficacy in de novo Renal Transplant Patients (Percent of Patients) at 6 and 12 Months of Treatment When Administered in Combination with Cyclosporine and Corticosteroids
| Endpoints | mycopheno lic acid(N=213) n (%) | MMF (N=210) n (%) | Difference in event rate (mycophen olic acid- MMF) | 95% CI (mycophen olic acid- MMF) | ||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Primary efficacy endpoint at Month 6 | ||||||||||
Biopsy-proven acute rejection episode, graft loss, death or lost to follow-up | 55 (25.8) | 55 (26.2) | -0.4% | (-8.7%, 8.0%) | ||||||
| Biopsy-proven acute rejection | 46 (21.6) | 48 (22.9) | -1.3% | ( -9.2%, 6.7%) | ||||||
| Graft loss or death | 8 (3.8) | 11 (5.2) | -1.5% | ( -5.4%, 2.5%) | ||||||
| Graft loss | 7 (3.3) | 9 (4.3) | -1.0% | ( -4.6%, 2.6%) | ||||||
| Death | 1 (0.5) | 2 (1.0) | -0.5% | -- | ||||||
| Lost to follow-up 1 | 3 (1.4) | 0 | 1.4% | -- | ||||||
| Efficacy endpoints at Month 12 | ||||||||||
Biopsy-proven acute rejection episode, graft loss, death or lost to follow-up | 61 (28.6) | 59 (28.1) | 0.5% | (-8.0%, 9.1%) | ||||||
| Graft loss, death or lost to follow-up | 20 (9.4) | 18 (8.6) | 0.8% | (-4.6%, 6.3%) | ||||||
| Biopsy-proven acute rejection | 48 (22.5) | 51 (24.3) | -1.8% | ( -9.8%, 6.3%) | ||||||
| Graft loss or death | 11 (5.2) | 14 (6.7) | -1.5% | ( -6.0%, 3.0%) | ||||||
| Graft loss | 9 (4.2) | 9 (4.3) | -0.1% | ( -3.9%, 3.8%) | ||||||
| Death | 2 (0.9) | 5 (2.4) | -1.4% | -- | ||||||
| Lost to follow-up 1 | 5 (2.3) | 0 | 2.3% | -- | ||||||
| 1 ‘Lost to follow-up’ endpoint calculated for the primary composite endpoint (biopsy-proven acute rejection, graft loss, death, or loss to follow-up). | ||||||||||
The maintenance study was conducted in 322 renal transplant patients (ages 18–75 years), who were at least 6 months post-transplant receiving 2 g/day MMF in combination with cyclosporine, with or without corticosteroids for at least four weeks prior to entry in the study. Patients were randomized to mycophenolic acid 1.44 g/day or MMF 2 g/day for 12 months. The efficacy endpoint was the incidence of biopsy-proven acute rejection, graft loss, death, or loss to follow-up at 6 and 12 months. The rates of biopsy-proven acute rejection, graft loss, death or loss to follow-up at 12 months were similar between mycophenolic acid and MMF-treated patients (Table 8).
Table 8: Efficacy in Maintenance Transplant Patients Parameters (Percent of Patients) at 6 and 12 Months of Treatment when Administered in Combination with Cyclosporine and with or without Corticosteroids
| Months 0 to 6 | Months 0 to 12 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Endpoint | mycoph enolic acid(N=1 59) n (%) | MMF (N=163) n (%) | mycoph enolic acid(N=1 59) n (%) | MMF (N=163) n (%) | |||||||||
| Biopsy-proven acute rejection episode, graft loss, death or lost to follow-up | 6 (3.8) | 10 (6.1) | 12 (7.5) | 20 (12.3) | |||||||||
| Biopsy-proven acute rejection, biopsy-proven chronic rejection, graft loss, death or lost to follow-up | 9 (5.7) | 11 (6.7) | 17 (10.7) | 22 (13.5) | |||||||||
| Graft loss, death or lost to follow-up | N/A | N/A | 10 (6.3) | 17 (10.4) | |||||||||
| Biopsy-proven acute rejection | 2 (1.3) | 2 (1.2) | 2 (1.3) | 5 (3.1) | |||||||||
| Acute rejection | 2 (1.3) | 3 (1.8) | 2 (1.3) | 6 (3.7) | |||||||||
| Treated acute rejection | 2 (1.3) | 2 (1.2) | 2 (1.3) | 3 (1.8) | |||||||||
| Acute rejections requiring antibody therapy | 0 | 0 | 0 | 0 | |||||||||
| Biopsy-proven chronic rejection | 4 (2.5) | 4 (2.5) | 6 (3.8) | 8 (4.9) | |||||||||
| Graft loss | 0 | 1 (0.6) | 0 | 1 (0.6) | |||||||||
| Death 1 | 0 | 1 (0.6) | 2 (1.3) | 4 (2.5) | |||||||||
| Lost to follow-up 2 | 4 (2.5) | 6 (3.7) | 8 (5.0) | 12 (7.4) | |||||||||
| Graft loss or death | 0 | 2 (1.2) | 2 (1.3) | 5 (3.1) | |||||||||
1 In addition, one patient (MMF group) withdrew consent on Day 273, and was discontinued from the study. Patient died post-study on Day 290. Patient was included in the composite variable as a ‘lost to follow-up’). 2 ‘Lost to follow-up’ endpoint calculated for the primary composite endpoint (biopsy-proven acute rejection, graft loss, death, or lost to follow-up. | |||||||||||||
14.3 Comparative Bioavailability Studies
Fasting Study
A double blinded, balanced, randomized, two-way, single-dose crossover bioequivalence study comparing MAR-MYCOPHENOLIC ACID delayed-release tablets, 360 mg (Marcan Pharmaceuticals Inc.) with PrMYFORTIC® enteric-coated tablets, 360 mg (Novartis Pharmaceuticals Canada Inc.) was conducted in 42 healthy adult male subjects under fasting conditions. The summary of the comparative bioavailability data is presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Mycophenolic acid (1 x 360 mg) Geometric mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
AUCT (mcg·h/mL) | 26.87 27.93(27.19) | 25.44 27.05 (29.75) | 105.62 | 97.83 - 114.04 |
AUCI (mcg·h/mL) | 28.53 31.10 (38.61) | 27.94 30.05 (30.45) | 102.10 | 95.35 - 109.32 |
Cmax (mcg/mL) | 16.57 17.43 (30.14) | 14.67 16.18 (38.90) | 112.99 | 101.23 - 126.11 |
Tmax3 (h) | 2.63 (1.25 – 5.33) | 2.75 (1.75 – 5.33) | ||
T½4 (h) | 13.12 (81.46) | 13.26 (72.52) | ||
1 MAR-MYCOPHENOLIC ACID (mycophenolic acid as mycophenolate sodium) delayed-release tablets, 360 mg (Marcan Pharmaceuticals Inc.).
2 PrMYFORTIC® (mycophenolic acid as mycophenolate sodium) enteric-coated-tablets, 360 mg (Novartis Pharmaceuticals Canada Inc.).
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV %) only
Fed Study
A double blinded, balanced, randomized, two-way, single-dose crossover bioequivalence study comparing MAR-MYCOPHENOLIC ACID delayed-release tablets, 360 mg (Marcan Pharmaceuticals Inc.) with PrMYFORTIC® enteric-coated tablets, 360 mg (Novartis Pharmaceuticals Canada Inc.) was conducted in 23 healthy adult male subjects under high fat, high calorie fed conditions. The summary of the comparative bioavailability data is presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Mycophenolic acid (1x 360 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
AUCT (mcg·h/mL) | 25.68 26.83 (34.90) | 25.22 26.09 (31.07) | 101.8 | 94.9-109.3 |
AUCI (mcg·h/mL) | 27.28 28.90 (42.91) | 27.13 28.19 (32.65) | 100.5 | 93.4-108.1 |
Cmax (mcg/mL) | 8.60 9.96 (48.10) | 6.75 7.78 (48.22) | 127.5 | 97.9-166.1 |
Tmax3 (h) | 9.00 (2.50 -20.00) | 11.00 (4.00 – 20.00) | - | - |
T½4 (h) | 11.50 (41.51) | 10.83 (40.94) | - | - |
1 MAR-MYCOPHENOLIC ACID (mycophenolic acid as mycophenolate sodium) delayed-release tablets, 360 mg (Marcan Pharmaceuticals Inc.).
2 PrMYFORTIC® (mycophenolic acid as mycophenolate sodium) enteric-coated-tablets, 360 mg (Novartis Pharmaceuticals Canada Inc.).
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV %) only.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Animal toxicity and pharmacology
The hematopoetic and lymphoid systems were the primary organs affected in toxicology studies conducted with mycophenolate sodium in rats and mice. Aplastic, regenerative anemia was identified as being the dose-limiting toxicity in rodents exposed to MPA. Evaluation of myelograms showed a marked decrease in erythroid cells (polychromatic erythroblasts and normoblasts) and a dose- dependent enlargement of the spleen and increase in extramedullary hematopoiesis. These effects occurred at systemic exposure levels which are equivalent to or less than the clinical exposure at the recommended dose of 1.44 g/day of mycophenolic acid in renal transplant patients.
The non-clinical toxicity profile of mycophenolate sodium appears to be consistent with adverse events observed in humans exposed to MPA, which now provide safety data of more relevance to the patient population (see 8 ADVERSE REACTIONS). Single oral doses of MPA are moderately well tolerated in rats (LD50 of 350-700 mg/kg), well tolerated in mice or monkeys (LD50 of more than 1000 mg/kg), and extremely well tolerated in rabbits (LD50 of more than 6000 mg/kg).
Carcinogenicity: In a 104-week oral carcinogenicity study in rats, mycophenolate sodium at daily doses up to 9mg/kg was not tumorigenic. The highest dose tested resulted in approximately 0.6-1.2 times the systemic exposure observed in renal transplant patients at the recommended dose of 1.44g/day.
Similar results were observed in a parallel study in rats performed with mycophenolate mofetil. In a 26-week oral carcinogenicity assay in a P53± (heterozygous) transgenic mouse model, mycophenolate sodium at daily doses up to 200 mg/kg was not tumorigenic. The highest dose tested was 200 mg/kg, resulting in approximately 5 times the systemic exposure observed in renal transplant patients (1.44 g/day)
Genotoxicity: The genotoxic potential of mycophenolate sodium was determined in five assays. MPA was genotoxic in the mouse lymphoma/thymidine kinase assay, the micronucleus test in V79 Chinese hamster cells and the in vivo mouse micronucleus assay. Mycophenolate sodium was not genotoxic in the bacterial mutation assay or the chromosomal aberration assay in human lymphocytes. The lowest dose showing genotoxic effects in a mouse bone marrow micronucleus resulted in approximately 3 times the systemic exposure (AUC or Cmax) observed in renal transplant patients at the tested clinical dose of 1.44 g of mycophenolic acid per day. It is probable that the mutagenic activity observed was due to a shift in the relative abundance of the nucleotides in the cellular pool used for DNA synthesis.
Reproductive and Developmental Toxicology: Mycophenolate sodium had no effect on fertility of male rats at oral doses up to 40 mg/kg/day. The systemic exposure at this dose represents approximately 9 times the clinical exposure at the tested clinical dose of 1.44 g of mycophenolic acid per day. No effects on female fertility were seen up to a dose of 20 mg/kg/day, a dose at which maternal toxicity and embryotoxicity were already observed.
In a teratology study performed with mycophenolate sodium in rats, at a dose as low as 1mg/kg, malformations in the offspring were observed, including anophthalmia, exencephaly and umbilical hernia. The systemic exposure at this dose represents 0.05 times the clinical exposure at the dose of
1.44 g/day of mycophenolic acid. In a pre- and postnatal development study in rat, mycophenolic acid (as sodium salt) caused developmental delays (abnormal pupillary reflex in females and preputial separation in males) at the highest dose of 3 mg/kg.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrMYFORTIC®, Mycophenolic acid enteric-coated tablets, 180 mg and 360 mg mycophenolic acid (as mycophenolate sodium), Control no. 289913, Product Monograph, Novartis Pharmaceuticals Canada Inc., January 29, 2025.