


Product Monograph - Methadose
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions | 03/2021 |
TABLE OF CONTENTS
TABLE OF CONTENTS ..............................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION ..........................................................4
1 INDICATIONS ..................................................................................................................4
1.1 Pediatrics ..................................................................................................................4
1.2 Geriatrics ..................................................................................................................4
2 CONTRAINDICATIONS .................................................................................................4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................5
4 DOSAGE AND ADMINISTRATION .............................................................................6
4.1 Dosing Considerations .............................................................................................6
4.2 Recommended Dose and Dosage Adjustment .........................................................7
4.4 Administration .........................................................................................................8
4.5 Missed Dose .............................................................................................................8
5 OVERDOSAGE .................................................................................................................9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ..............10
7 WARNINGS AND PRECAUTIONS .............................................................................10
7.1 Special Populations ................................................................................................18
7.1.1 Pregnant Women ....................................................................................................18
7.1.2 Breastfeeding .........................................................................................................20
7.1.3 Pediatrics ................................................................................................................21
7.1.4 Geriatrics ................................................................................................................21
8 ADVERSE REACTIONS ................................................................................................21
8.1 Adverse Reaction Overview ..................................................................................21
8.5 Post-Market Adverse Reactions .............................................................................23
9 DRUG INTERACTIONS ................................................................................................24
9.1 Serious Drug Interactions ......................................................................................24
9.2 Drug Interactions Overview ...................................................................................24
9.3 Drug-Behavioural Interactions...............................................................................26
9.4 Drug-Drug Interactions ..........................................................................................26
9.5 Drug-Food Interactions ..........................................................................................28
9.6 Drug-Herb Interactions ..........................................................................................29
9.7 Drug-Laboratory Test Interactions ........................................................................29
10 CLINICAL PHARMACOLOGY ...................................................................................29
10.1 Mechanism of Action .............................................................................................29
10.2 Pharmacodynamics ................................................................................................29
10.3 Pharmacokinetics ...................................................................................................30
11 STORAGE, STABILITY AND DISPOSAL .................................................................33
12 SPECIAL HANDLING INSTRUCTIONS ....................................................................33
PART II: SCIENTIFIC INFORMATION ................................................................................34
13 PHARMACEUTICAL INFORMATION ......................................................................34
15 MICROBIOLOGY ..........................................................................................................34
16 NON-CLINICAL TOXICOLOGY ...............................................................................34
PATIENT MEDICATION INFORMATION ...........................................................................38
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
METHADOSE is indicated for substitution treatment in opioid drug dependence in adults.
METHADOSE is not indicated as an as-needed (prn) analgesic.
Patients prescribed METHADOSE should be carefully monitored within a framework of medical, social and psychological support as part of a comprehensive opioid dependence treatment program.
- 1.1 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of METHADOSE has not been studied in the pediatric population. Therefore the use of METHADOSE is not recommended in patients under 18 years of age.
- 1.2 Geriatrics
Geriatrics (>65 years of age): The safety and effectiveness of METHADOSE in patients 65 years of age or older have not been established. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
2 CONTRAINDICATIONS
- Patients who are hypersensitive to the active substance methadone hydrochloride or other opioid analgesics or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the Product Monograph.
- In patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- METHADOSE should not be given to patients with diarrhea associated with pseudomembranous colitis or caused by poisoning, until toxic material has been eliminated from the gastrointestinal tract.
- Patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- Patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus.
- Patients with acute respiratory depression, elevated carbon dioxide levels in the blood and cor pulmonale.
- Patients with acute alcoholism, delirium tremens, and convulsive disorders.
- Patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- Patients taking monoamine oxidase (MAO) inhibitors (or within 14 days of such therapy).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Addiction, Abuse, and Misuse
METHADOSE poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing METHADOSE, and all patients should be monitored regularly for the development of these behaviours or conditions (see WARNINGS AND PRECAUTIONS). METHADOSE should be stored securely to avoid theft or misuse.
Life-Threatening Respiratory Depression: OVERDOSE
Serious, life-threatening, or fatal respiratory depression may occur with use of METHADOSE. Infants exposed in utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of METHADOSE or following a dose increase. Further, instruct patients of the hazards related to taking opioids including fatal overdose.
Deaths have been reported during initiation of methadone treatment for opioid dependence. In some cases, drug interactions with other drugs, both licit and illicit, have been suspected. However, in other cases, deaths appear to have occurred due to the respiratory or cardiac effects of methadone and too-rapid titration without appreciation for the accumulation of methadone over time. It is critical to understand the pharmacokinetics of methadone and to exercise vigilance during treatment initiation and dose titration (see DOSAGE AND ADMINISTRATION). Patients must also be strongly cautioned against self-medicating with central nervous system (CNS) depressants during initiation of methadone treatment.
Respiratory depression is the chief hazard associated with methadone hydrochloride administration. Methadone’s peak respiratory depressant effects are typically delayed. This characteristic can contribute to cases of iatrogenic overdose, particularly during treatment initiation and dose titration.
QT Interval Prolongation
Cases of QT interval prolongation and serious arrhythmia (torsades de pointes) have been observed during treatment with methadone. Most cases involve patients being treated for pain with large, multiple daily doses of methadone, although cases have been reported in patients receiving doses commonly used for maintenance treatment of opioid addiction.
Accidental Exposure
Accidental ingestion of even one dose of METHADOSE, especially by children, can result in a fatal overdose of methadone hydrochloride (see DOSAGE AND ADMINISTRATION).
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of METHADOSE during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see WARNINGS AND PRECAUTIONS).
Interaction with Alcohol
The co-ingestion of alcohol with METHADOSE should be avoided as it may result in dangerous additive effects, causing serious injury or death (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
Risks From Concomitant Use with Benzodiazepines or Other CNS Depressants
Concomitant use of opioids with benzodiazepines or other CNS depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
- Reserve concomitant prescribing of METHADOSE and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Patients prescribed methadone should be carefully monitored and provided appropriate supportive psychological and social services.
Methadone differs from many other opioid agonists in several important ways. Methadone’s pharmacokinetic properties, coupled with high inter-patient variability in its absorption, metabolism, and relative analgesic potency, necessitate a cautious and highly individualized approach to prescribing. Particular vigilance is necessary during treatment initiation, during conversion from one opioid to another, and during dose titration.
The complexities associated with methadone dosing can contribute to cases of iatrogenic overdose, particularly during treatment initiation and dose titration. A high degree of “opioid tolerance” does not eliminate the possibility of methadone overdose, iatrogenic or otherwise. Deaths have been reported during conversion to methadone from chronic, high-dose treatment with other opioid agonists and during initiation of methadone treatment of addiction in subjects previously abusing high doses of other agonists.
After interruption of chronic dosing, if methadone treatment is to be continued, re-starting doses should be low and patients should be titrated slowly to effect in order to avoid severe toxicity and respiratory depression.
4.2 Recommended Dose and Dosage Adjustment
The initial METHADOSE dose should be administered, under supervision, when there are no signs of sedation or intoxication, and the patient shows symptoms of withdrawal. The dosage schedules indicated below are recommended but could be varied in accordance with clinical judgment. Initially, a single dose of 20 to 30 mg of METHADOSE will often be sufficient to suppress withdrawal symptoms. The initial dose should not exceed 30 mg. If same-day dosing adjustments are to be made, the patient should be asked to wait 2 to 4 hours for further evaluation, when peak levels have been reached. An additional 5 to 10 mg of METHADOSE may be provided if withdrawal symptoms have not been suppressed or if symptoms reappear. The total daily dose of METHADOSE on the first day of treatment should not ordinarily exceed 40 mg.
Over the first week of treatment, dose adjustments should be made based on control of withdrawal symptoms at the time of expected peak analgesic activity (e.g., 2 to 4 hours after dosing). Prescribers are reminded that methadone’s peak respiratory depressant effects typically occur later, and persist longer, than its peak analgesic effects. Dose adjustment should be cautious; deaths have occurred in early treatment due to the cumulative effects of the first several days’ dosing. Patients should be reminded that the dose will “hold” for a longer period of time as tissue stores of methadone accumulate.
Patients Not Receiving Opioids at the Time of Initiation of Methadone Treatment:
Initial doses should be lower for patients whose tolerance is expected to be low at treatment entry. Loss of tolerance should be considered in any patient who has not taken opioids for more than 5 days. Initial doses should not be determined by previous treatment episodes or dollars spent per day on illicit drug use.
Methadone Substitution Use: Maintenance Treatment or Detoxification Treatment:
Methadone may be used in a maintenance treatment program of varying duration, or in a short-term detoxification protocol of gradually decreasing doses to the point of abstinence. Patients may remain in methadone maintenance treatment indefinitely, or may be ready for a medically-supervised taper at some point. Regardless of maintenance or detoxification treatment, increased risk of relapse following withdrawal of methadone treatment should be considered.
Prescribers are referred to clinical practice treatment standards and guidelines in their area.
Special Considerations for a Pregnant Woman:
Caution should be taken in the maintenance treatment of pregnant patients. For opioid-dependent pregnant women, methadone maintenance should be provided at the lowest accepted dose which prevents withdrawal symptoms (usually less than 80 mg/day). In later pregnancy, it may be necessary to increase the dose, as increased clearance and reduced plasma levels have been reported during pregnancy (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women). An increase by 10 - 20 mg and/or divided dose may be required.
Treatment should be provided throughout pregnancy to protect the fetus and for a minimum of six months postpartum.
Patients with Hepatic Impairment:
Dosage adjustments should be based on the patient’s clinical response (see WARNINGS AND PRECAUTIONS).
Patients with Renal Impairment:
Dosage adjustments should be based on the patient’s clinical response (see WARNINGS AND PRECAUTIONS).
Geriatrics:
Dosage adjustments should be based on the patient’s clinical response (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
Adjustment or Reduction of Dosage:
Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including METHADOSE. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.
Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer desired or required for methadone maintenance treatment. Tapering should be individualized to the patient and carried out under medical supervision.
Patient should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
4.4 Administration
USUAL ADULT DOSE: To be determined by the physician; may be diluted with water or other liquid before oral administration.
METHADOSE should be kept in a safe place, out of the sight and reach of children before, during and after use. METHADOSE should not be used in front of children, since they may copy these actions.
4.5 Missed Dose
If the patient forgets to take one or more doses, they should take their next dose at the next scheduled time and in the normal amount.
5 OVERDOSAGE
For management of a suspected drug overdose, contact your regional poison control centre.
Signs and Symptoms
Serious overdosage of methadone is characterized by respiratory depression (a decrease in respiratory rate and/or tidal volume, Cheyne-Stokes respiration, cyanosis), extreme somnolence progressing to stupor or coma, maximally constricted pupils, skeletal-muscle flaccidity, cold and clammy skin, and sometimes, bradycardia and hypotension. In severe overdosage, particularly by the intravenous route, apnea, circulatory collapse, cardiac arrest, and death may occur.
Other important adverse events reported with methadone overdose (acute or chronic) include sudden sensorial hearing loss, toxic leukoencephalopathy, rhabdomyolysis progressing to renal failure, serotonin syndrome, and hypoglycemia.
Treatment
Primary attention should be given to the reestablishment of adequate respiratory exchange through provision of a patent airway and institution of assisted or controlled ventilation. If a non-tolerant person takes a large dose of methadone, effective opioid antagonists are available to counteract the potentially lethal respiratory depression. The physician must remember, however, that methadone is a long-acting depressant (36 to 48 hours), whereas opioid antagonists act for much shorter periods (one to three hours). The patient must, therefore, be monitored continuously for recurrence of respiratory depression and may need to be treated repeatedly with the narcotic antagonist.
Opioid antagonists should not be administered in the absence of clinically significant respiratory or cardiovascular depression. In an individual physically dependent on opioids, the administration of the usual dose of an opioid antagonist may precipitate an acute withdrawal syndrome. The severity of this syndrome will depend on the degree of physical dependence and the dose of the antagonist administered. If antagonists must be used to treat serious respiratory depression in the physically dependent patient, the antagonist should be administered with extreme care and by titration with smaller than usual doses of the antagonist. Intravenously administered naloxone or nalmefene may be used to reverse signs of intoxication. Because of the relatively short half-life of naloxone as compared with methadone, repeated injections may be required until the status of the patient remains satisfactory. Naloxone may also be administered by continuous intravenous infusion.
Oxygen, intravenous fluids, vasopressors, and other supportive measures should be employed as indicated.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients |
| Oral | Oral concentrate, cherry flavor: 10 mg/mL Oral concentrate, dye-free, sugar-free, unflavored: 10 mg/mL | METHADOSE Oral Concentrate contains: artificial cherry flavor, citric acid anhydrous, FD&C Red No. 40, D&C Red No. 33, methylparaben, poloxamer 407, propylene glycol, propylparaben, purified water, sodium citrate dihydrate, sucrose. METHADOSE Sugar-Free Oral Concentrate contains: citric acid anhydrous, purified water, and sodium benzoate. |
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
METHADOSE and METHADOSE Sugar-Free are for oral administration only. The preparation must not be injected. METHADOSE and METHADOSE Sugar-Free, if dispensed, should be packaged in child-resistant containers and kept out of reach of children to prevent accidental ingestion.
Methadone Hydrochloride, a synthetic opioid, is a controlled substance (Classification N) under the Controlled Drugs and Substances Act (CDSA).
Patients should be instructed not to give METHADOSE (methadone hydrochloride) to anyone other than the patient for whom it was prescribed, as such inappropriate use may have severe medical consequences, including death. METHADOSE should be stored securely to avoid theft or misuse.
METHADOSE should only be prescribed by persons knowledgeable in the continuous administration of potent opioids and in the detection and management of respiratory depression, including the use of opioid antagonists.
Patients should be cautioned not to consume alcohol while taking METHADOSE as it may increase the chance of experiencing serious adverse events, including death.
Abuse and Misuse:
Like all opioids, METHADOSE is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, METHADOSE should be prescribed and handled with caution. In addition, parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed METHADOSE. All patients receiving METHADOSE should be routinely monitored for signs of misuse and abuse.
METHADOSE is sought by people with addiction to opioids and is subject to diversion. This should be considered when prescribing METHADOSE in situations when the clinician is concerned about an increased risk of misuse, abuse, or diversion. Prescribe and dispense METHADOSE with appropriate precautions to minimize risk of misuse, abuse, or diversion, and ensure appropriate protection from theft, including in the patient’s home.
Methadone is a µ-agonist opioid with an abuse liability similar to that of morphine and other opioid agonists and is a Schedule I controlled substance. Methadone, like morphine and other opioids, has the potential for being abused and is subject to criminal diversion.
Use in Drug and Alcohol Addiction:
Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to METHADOSE unless used under extreme caution and awareness.
Incomplete Cross-Tolerance Between Methadone and Other Opioids:
Patients tolerant to other opioids may be incompletely tolerant to methadone. Incomplete cross-tolerance is of particular concern for patients tolerant to other µ-opioid agonists who are being converted to methadone, thus making determination of dosing during opioid conversion complex. Deaths have been reported during conversion from chronic, high-dose treatment with other opioid agonists. A high degree of “opioid tolerance” does not eliminate the possibility of methadone overdose, iatrogenic or otherwise.
Patients Experiencing Acute Pain:
Patients in methadone maintenance treatment for opioid dependence who experience physical trauma, postoperative pain or other acute pain cannot be expected to derive analgesia from their existing dose of METHADOSE. Such patients should be administered analgesics, including opioids, in doses that would otherwise be indicated for non-methadone-treated patients with similar painful conditions. Due to the opioid tolerance induced by methadone, when opioids are required for management of acute pain in methadone patients, somewhat higher and/or more frequent doses will often be required than would be the case for non-tolerant patients.
Neonatal Opioid Withdrawal Syndrome (NOWS):
Special care is required for the infant born to a mother who has been dependent on methadone and/or other opioids. Newborn infants who have been exposed to opioids in uteri within four weeks of delivery are potentially dependent and must be closely observed for withdrawal symptoms for at least two weeks. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Sign of neonatal opioid withdrawal syndrome include: irritability, hyperactivity and abnormal sleep pattern, increased respiratory rate, excessive or high pitched crying, tremor, vomiting, diarrhea, sneezing, yawning, fever and failure to gain weight. The onset and severity of the syndrome can vary, along with the duration which may range from a few days to weeks or even months. This variability is due to the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
The contribution of maternal methadone dose to the development of NOWS is not clear at present, as there are conflicting results. Some studies support an association, while others do not. In addition, there is currently no consensus on the appropriate management of infant withdrawal.
Monoamine Oxidase Inhibitors (MAOIs):
Severe and unpredictable reactions have been reported with concomitant use of MAOIs and opioid analgesics. Therefore, the use of methadone is not recommended in patients taking MAOIs (or within 14 days of such therapy). If the use of METHADOSE is necessary in such patients, a sensitivity test should be performed in which incremental doses of METHADOSE are administered over the course of several hours while the patient’s condition and vital signs are under careful observation (see also DRUG INTERACTIONS, Drug Interactions Overview).
Carcinogenesis and Mutagenesis
See NON-CLINICAL TOXICOLOGY section.
Cardiovascular
This information is intended to alert the prescriber to comprehensively evaluate the risks and benefits of methadone treatment. The intent is not to deter the appropriate use of methadone in patients with a history of cardiac disease.
Laboratory studies, both in vivo and in vitro, have demonstrated that methadone inhibits cardiac potassium channels and prolongs the QT interval. Cases of QT interval prolongation and serious arrhythmia (torsades de pointes) have been observed during treatment with methadone. These cases appear to be more commonly associated with, but not limited to, higher dose treatment (> 200 mg/day). Although most cases involve patients being treated for pain with large, multiple daily doses of methadone, cases have been reported in patients receiving doses commonly used for maintenance treatment of opioid addiction. In most of the cases seen at typical maintenance doses, concomitant medications and/or clinical conditions such as hypokalemia were noted as contributing factors. However, the evidence strongly suggests that methadone possesses the potential for adverse cardiac conduction effects in some patients.
Methadone should be administered with particular caution to patients already at risk for development of prolonged QT interval (e.g., cardiac hypertrophy, concomitant diuretic use, hypokalemia, hypomagnesemia). Careful monitoring is recommended when using methadone in patients with a history of cardiac conduction abnormalities, those taking medications affecting cardiac conduction, and in other cases where history or physical exam suggest an increased risk of dysrhythmia. QT prolongation has also been reported in patients with no prior cardiac history who have received high doses of methadone. Patients developing QT prolongation while on methadone treatment should be evaluated for the presence of modifiable risk factors, such as concomitant medications with cardiac effects, drugs which might cause electrolyte abnormalities and drugs which might act as inhibitors of methadone metabolism.
The potential risks of methadone, including the risk of life-threatening arrhythmias, should be weighed against the risks of discontinuing methadone treatment. In the patient being treated for opioid dependence with methadone maintenance therapy, these risks include a very high likelihood of relapse to illicit drug use following methadone discontinuation.
The use of methadone in patients already known to have a prolonged QT interval has not been systematically studied. The potential risks of methadone should be weighed against the substantial morbidity and mortality associated with untreated opioid addiction.
When treating patients with methadone, an individualized benefit to risk assessment should be carried out and should include evaluation of patient presentation and complete medical history. For patients judged to be at risk, careful monitoring of cardiovascular status, including evaluation of QT prolongation and dysrhythmias should be performed.
Methadone administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or concurrent administration of drugs such as phenothiazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics. These patients should be monitored for signs of hypotension after initiating or titrating the dose of METHADOSE.
Patients who are ambulatory should be cautioned that METHADOSE, like other opioids, may produce orthostatic hypotension.
The use of METHADOSE in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure.
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of METHADOSE and there is a potential for development of psychological dependence.
Physical dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid, and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning (see ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
Driving and Operating Machinery
METHADOSE may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of methadone with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Endocrine and Metabolism
Adrenal Insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Gastrointestinal
Methadone and other morphine-like opioids have been shown to decrease bowel motility. Methadone may obscure the diagnosis or clinical course of patients with acute abdominal conditions (see CONTRAINDICATIONS).
Hepatic/biliary/pancreatic
Methadone is metabolized in the liver and therefore patients with liver impairment may be at risk of accumulating methadone after multiple dosing. The use of METHADOSE has not been extensively evaluated in patients with hepatic insufficiency (see CLINICAL PHARMACOLOGY).
Caution should be used as methadone may precipitate porto-systemic encephalopathy in patients with severe liver damage.
As with other opioids, methadone may cause troublesome constipation, which is particularly dangerous in patients with severe hepatic impairment, and measures to avoid constipation should be initiated early.
Monitoring and laboratory tests
Methadone may interfere with urine testing for pregnancy.
Neurologic
Interactions with Central Nervous System Depressants (Including Benzodiazepines and Alcohol): METHADOSE should be used with caution and in a reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedative-hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, centrally-active anti-emetics and other CNS depressants. Respiratory depression, hypotension and profound sedation, coma or death may result. When such combination therapy is contemplated, a substantial reduction in the dose of one or both agents should be considered and patients should be carefully monitored. METHADOSE should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects (see DRUG INTERACTIONS).
Deaths have been reported when methadone has been abused in conjunction with benzodiazepines. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics (see DRUG INTERACTIONS). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when METHADOSE is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see DRUG INTERACTIONS).
METHADOSE should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see CONTRAINDICATIONS and DRUG INTERACTIONS).
Head Injury: The respiratory depressant effects of methadone, and the capacity to elevate cerebrospinal fluid pressure, may be greatly increased in the presence of an already elevated intracranial pressure produced by trauma. Also, methadone may produce confusion, miosis, vomiting and other side effects which obscure the clinical course of patients with head injury. In such patients, methadone must be used with extreme caution and only if it is judged essential (see CONTRAINDICATIONS).
Serotonin Toxicity/Serotonin Syndrome: Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with methadone, including METHADOSE, particularly during combined use with other serotonergic drugs (see DRUG INTERACTIONS).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g., tachycardia, flushing) and altered mental state (e.g., anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus.
- Inducible clonus or ocular clonus with agitation or diaphoresis.
- Tremor and hyperreflexia.
- Hypertonia and body temperature > 38°C and ocular clonus or inducible clonus.
If concomitant treatment with METHADOSE and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see DRUG INTERACTIONS). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Psychiatric
Since methadone as used by tolerant patients at a constant maintenance dosage does not act as a tranquilizer, patients will react to life problems and stresses with the same symptoms of anxiety as do other individuals. The physician should not confuse such symptoms with those of narcotic abstinence and should not attempt to treat anxiety by increasing the dose of METHADOSE. The action of methadone in maintenance treatment is limited to the control of narcotic withdrawal symptoms and is ineffective for relief of general anxiety.
Renal
The use of METHADOSE has not been extensively evaluated in patients with renal insufficiency (see CLINICAL PHARMACOLOGY).
Urine acidification has been shown to increase renal elimination of methadone.
Reproductive Health: Female and Male Potential
- Fertility
Reproductive function in human males may be decreased by methadone treatment. Reductions in ejaculate volume and seminal vesicle and prostate secretions have been reported in methadone-treated individuals. In addition, reductions in serum testosterone levels and sperm motility, and abnormalities in sperm morphology have been reported.
Long-term use of opioids may be associated with decreased sex hormone levels and symptoms such as low libido, erectile dysfunction, or infertility (see ADVERSE REACTIONS, Post-Market Adverse Reactions).
Published animal studies provide additional data indicating that methadone treatment of males can alter reproductive function. Methadone produces a significant regression of sex accessory organs and testes of male mice and rats. Additional data have been published indicating that methadone treatment of male rats increases death rate of embryos and neonates.
Respiratory
Respiratory Depression: Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status. Methadone should be used with extreme caution in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia (see CONTRAINDICATIONS).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of METHADOSE, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with METHADOSE and following dose increases.
Life-threatening respiratory depression is more likely to occur in the elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
Methadone’s peak respiratory depressant effects are typically delayed following intake. These characteristics can contribute to cases of iatrogenic overdose, particularly during treatment initiation and dose titration.
Use in Patients with Chronic Pulmonary Disease: Monitor patients with significant chronic obstructive pulmonary disease or cor pulmonale, and patients having a substantially decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression for respiratory depression, particularly when initiating therapy and titrating with METHADOSE, as in these patients, even usual therapeutic doses of METHADOSE may decrease respiratory drive to the point of apnea. In these patients, use of alternative non-opioid analgesics should be considered, if possible. The use of METHADOSE is contraindicated in patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus (see CONTRAINDICATIONS).
Sleep Apnea: Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia) (see ADVERSE REACTIONS). Opioid use increases the risk of CSA in a dose dependent fashion. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider reducing or stopping the opioid treatment if appropriate, using best practices for tapering of opioids (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment; WARNINGS AND PRECAUTIONS).
7.1 Special Populations
Special Risk Groups: METHADOSE should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
Gender
The use of METHADOSE has not been evaluated for gender specificity.
7.1.1 Pregnant Women
Although methadone crosses the placental barrier, reproduction studies in humans have not been conducted.
It is the physician’s responsibility to ensure that female patients are fully informed concerning the possible risks to a pregnant woman or her unborn child from both the use of methadone, and stopping the use of methadone. Care of pregnant patients should be under the supervision of a physician experienced in the management of this patient population in opioid addiction.
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS, Post-Market Adverse Reactions).
Animal reproduction studies have revealed no evidence of harm to the fetus due to methadone.
Gestation:
Methadone has been detected in amniotic fluid and cord plasma at concentrations proportional to maternal plasma and in newborn urine at lower concentrations than corresponding maternal urine. Methadone and its primary metabolite have been detected in samples of meconium.
A retrospective series of 101 pregnant, opioid-dependent women who underwent in-patient opioid detoxification with methadone did not demonstrate any increased risk of miscarriage in the second trimester or premature delivery in the third trimester.
Abnormal fetal non-stress tests (NSTs) have been reported to occur more frequently when the test is performed 1 to 2 hours after a maintenance dose of methadone in late pregnancy compared to controls. Fetuses of methadone maintained mothers show decreased fetal heart rate and motor activity.
Several studies have suggested that infants born to opioid-abusing women treated with methadone during all or part of pregnancy have been found to have decreased fetal growth with reduced birth weight, length, and/or head circumference compared to controls. This growth deficit does not appear to persist into later childhood.
Additional information on the potential risks of methadone may be derived from animal data (NON-CLINICAL TOXICOLOGY).
Perinatal:
Studies show methadone exposure to be associated with an increased risk of very pre-term birth (< 32 weeks of gestation), being small for gestational age (< 10th percentile), admission to the neonatal unit, and diagnosis of a major congenital anomaly. With increasing maternal methadone dose, there may be a corresponding increase in infants’ risk of being born pre-term, being symmetrically smaller, spending longer periods in hospital and the need for treatment for Neonatal Abstinence Syndrome.
Neonatal Growth and Development:
There are conflicting reports on whether SIDS (Sudden Infant Death Syndrome) occurs with an increased incidence in infants born to women treated with methadone during pregnancy.
Studies show opioid exposure in utero has an effect on the development of the brain and visual system. Lower performance on tests of cognitive function and neurodevelopmental abnormalities have been found in some, although not all, studies and children have been shown to demonstrate mild, but persistent deficits in performance on psychometric and behavioral tests. It is unclear whether these differences in performance are caused by the direct effects of in utero exposure to methadone, whether they are caused indirectly by genetic and environmental risk factors, or are a consequence of pre-term birth.
Published animal studies suggest that perinatal exposure to opioids including methadone may alter neuronal development and behaviour in the offspring. Perinatal methadone exposure in rats has been linked to alterations in learning ability, motor activity, thermal regulation, nociception responses and sensitivity to other drugs. Additional animal data demonstrates evidence for neurochemical changes in the brains of methadone-treated offspring, including the cholinergic, dopaminergic noradrenergic and serotonergic systems. Published animal data have reported increased neonatal mortality and significant differences in behavioral tests in the offspring of male rats that were treated with methadone prior to mating. Mechanistic studies in this rat model suggest that the developmental effects of “paternal” methadone on the progeny may be due to decreased testosterone production; decreased testosterone levels reported in men on methadone maintenance therapy.
Ophthalmic Abnormalities:
Infants born to drug-misusing mothers prescribed methadone in pregnancy are at risk of a range of visual problems, the underlying causes of which are not clear. Ophthalmic abnormalities included reduced acuity, nystagmus, delayed visual maturation, strabismus, refractive errors, and cerebral visual impairment. Those infants with Neonatal Abstinence Syndrome severe enough to receive pharmaceutical treatment may be at particular risk of developing nystagmus. Delayed visual development has also been reported. Exposure to opioid including methadone, during pregnancy may result in permanently reduced vision and nystagmus.
Labour, Delivery and Nursing Women:
As with all opioids, administration of this product to the mother shortly before delivery may result in some degree of respiratory depression in the newborn, especially if higher doses are used. Naloxone, a drug that counters the effects of opioids, should be readily available if METHADOSE is used in this population. METHADOSE is not recommended for obstetric analgesia because its long duration of action increases the probability of respiratory depression in the newborn. Narcotics with mixed agonist/antagonist properties should not be used for pain control during labor in patients chronically treated with METHADOSE as they may precipitate acute withdrawal.
7.1.2 Breastfeeding
Methadone is secreted into human milk. Caution should be exercised when METHADOSE is administered to a nursing woman. There have been rare cases of sedation, respiratory depression, and death in infants exposed to methadone through breast milk.
The evaluation of the risks and benefits of breastfeeding while on methadone maintenance therapy should be done jointly by the physician and the patient. Patients who express a desire to breastfeed should clearly understand why they should not use illicit substances or any other drug not prescribed by their health professional while breastfeeding and how the use of additional drugs can pose additional risks to the breastfeeding infant beyond those associated with METHADOSE.
Mothers using METHADOSE should receive specific information about how to identify respiratory depression and sedation in their babies. They should know when to contact a health professional or seek immediate medical care.
At maternal oral doses of 10 to 80 mg/day, methadone concentrations from 50 to 570 mcg/L in milk have been reported, which, in the majority of samples, were lower than maternal serum drug concentrations at steady state. Peak methadone levels in milk occur approximately 4 to 5 hours after an oral dose. Based on an average milk consumption of 150 mL/kg/day, an infant would consume approximately 17.4 mcg/kg/day, which is approximately 2 to 3% of the oral maternal dose. Methadone has been detected in very low plasma concentrations in some infants whose mothers were taking methadone.
Women being treated with METHADOSE for any indication who are already breastfeeding should be counseled to wean breastfeeding gradually in order to prevent the development of withdrawal symptoms in the infant.
7.1.3 Pediatrics
The safety and efficacy of METHADOSE have not been studied in the pediatric population. Therefore, use of METHADOSE is not recommended in patients under 18 years of age.
Ingestion by a child, whether accidental or deliberate, is a medical emergency that may result in death. Patients with take-home doses should be instructed to keep METHADOSE in a secure place out of the reach and sight of children and to discard unused METHADOSE in such a way that individuals other than the patient for whom it was originally prescribed will not come in contact with the drug.
7.1.4 Geriatrics
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range and titrate slowly, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION and CLINICAL PHARMACOLOGY).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse effects of METHADOSE are similar to those of other opioid analgesics, and represent an extension of pharmacological effects of the drug class. The major hazards of opioids include respiratory and central nervous system depression and to a lesser degree, circulatory depression, respiratory arrest, shock and cardiac arrest.
Heroin Withdrawal:
During the induction phase of methadone maintenance treatment, patients are being withdrawn from heroin and may therefore show typical withdrawal symptoms, which should be differentiated from methadone-induced side effects. They may exhibit some or all of the following signs and symptoms associated with acute withdrawal from heroin or other opioids: lacrimation, rhinorrhea, sneezing, yawning, excessive perspiration, gooseflesh, fever, chilliness alternating with flushing, restlessness, irritability, weakness, anxiety, depression, dilated pupils, tremors, tachycardia, abdominal cramps, body aches, involuntary twitching and kicking movements, anorexia, nausea, vomiting, diarrhea, intestinal spasms, and weight loss.
Initial Administration:
The initial METHADOSE dose should be carefully titrated to the individual. Too rapid titration for the patient’s sensitivity is more likely to produce adverse effects.
The major hazards of methadone are respiratory depression, QT interval prolongation and systemic hypotension. Respiratory arrest, shock, cardiac arrest, and death have occurred. Patients may be particularly vulnerable during the stabilization period (see WARNINGS AND PRECAUTIONS).
Maintenance on a Stabilized Dose:
During prolonged administration of METHADOSE, as in a methadone maintenance treatment program, there is usually a gradual, yet progressive, disappearance of side effects over a period of several weeks. However, constipation and sweating often persist.
The most frequently observed adverse reactions include lightheadedness, dizziness, sedation, nausea, vomiting, constipation and sweating.
Constipation: Practically all patients become constipated while taking opioids on a persistent basis. In some patients, particularly the elderly or bedridden, fecal impaction may result. It is essential to caution the patients in this regard and to institute an appropriate regimen of bowel management at the start of prolonged opioid therapy. Stimulant laxatives, stool softeners, and other appropriate measures should be used as required. As fecal impaction may present as overflow diarrhea, the presence of constipation should be excluded in patients on opioid therapy prior to initiating treatment for diarrhea.
Adverse Drug Reactions
Cardiac Disorders (see WARNINGS AND PRECAUTIONS): arrhythmias, bigeminal rhythms, bradycardia, cardiomyopathy, extrasystoles, flushing, heart failure, hypotension, palpitations, phlebitis, syncope, tachycardia, torsades de pointes, ventricular fibrillation, ventricular tachycardia
Eye Disorders: visual disturbances
Gastrointestinal Disorders: abdominal pain, constipation, dry mouth, glossitis, nausea, vomiting
General Disorders and Administration Site Conditions: asthenia (weakness), edema
Hepatobiliary Disorders: biliary colic
Investigations: ECG abnormal, Electrocardiogram QT prolonged, T-wave inversion
Metabolic and Nutritional Disorders: anorexia, hypokalemia, hypomagnesemia, weight gain
Nervous System Disorders: dizziness, headache, lightheadedness, sedation, sleep-disordered breathing, seizures
Psychiatric Disorders: hallucinations, agitation, confusion, disorientation, dysphoria, euphoria, insomnia
Renal and Urinary Disorders: antidiuretic effect, urinary retention or hesitancy
Reproductive System and Breast Disorders: amenorrhea, reduced libido and/or potency
Respiratory, Thoracic and Mediastinal Disorders: pulmonary edema, respiratory depression (see WARNINGS AND PRECAUTIONS)
Skin and Subcutaneous Tissue Disorders: pruritis, urticaria, other skin rashes, and rarely, hemorrhagic urticaria
Abnormal Hematologic and Clinical Chemistry Findings
Reversible thrombocytopenia has been described in patients with chronic hepatitis.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of METHADOSE.
Endocrine Disorders: androgen deficiency
Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Metabolic and Nutritional Disorders: Hypoglycemia
Nervous System Disorders: serotonin syndrome
Pregnancy, Puerperium and Perinatal Conditions: neonatal opioid withdrawal syndrome (NOWS)
General Disorders and Administration Site Conditions: drug ineffective
Isolated reports have been received for drug ineffectiveness following a switch between different methadone products. The current data are insufficient to support an estimate of the incidence or to establish causation. Patients presenting with symptoms of withdrawal following formulation change should be clinically monitored and dose titrated as needed.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
- CNS Depressants
- MAOIs
- Serotonergic Drugs (including SSRIs)
- Potentially Arrhythmogenic Agents
(See Drug-Drug Interactions.)
9.2 Drug Interactions Overview
Effects of CYP Inhibitors and Inducers:
In vitro results suggest that methadone undergoes hepatic N-demethylation by cytochrome P450 enzymes, principally CYP3A4, CYP2B6, CYP2C19, and to a lesser extent by CYP2C9 and CYP2D6. Co-administration of methadone with inducers of these enzymes may result in a more rapid metabolism and potential for decreased effects of methadone, whereas administration with CYP inhibitors may reduce metabolism and potentiate methadone’s effects. Although anti- retroviral drugs such as efavirenz, nelfinavir, nevirapine, ritonavir, and lopinavir + ritonavir combination are known to inhibit CYPs, they are shown to reduce the plasma levels of methadone, possibly due to their CYP induction activity.
Therefore, drugs administered concomitantly with methadone should be evaluated for interaction potential; clinicians are advised to evaluate individual response to drug therapy (see also Drug-Herb Interactions).
Interactions with Central Nervous System (CNS) Depressants (Including Benzodiazepines and Alcohol):
Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants (e.g., other opioids, sedatives/hypnotics, antidepressants, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, phenothiazines, neuroleptics, antihistamines, anti-emetics, and alcohol) and beta-blockers, increases the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation (see WARNINGS AND PRECAUTIONS). METHADOSE should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
Monoamine Oxidase Inhibitors (MAOIs):
Severe and unpredictable reactions have been reported with concomitant use of MAOIs and opioid analgesics. Since the safety of methadone in this regard has not been established, the use of methadone in patients who have received MAOIs during the previous 14-day period is not recommended. However, if the use of METHADOSE is necessary in such patients, a sensitivity test should be performed in which incremental doses of METHADOSE are administered over the course of several hours while the patient’s condition and vital signs are under careful observation (see also WARNINGS AND PRECAUTIONS).
Serotonergic Drugs:
Some selective serotonin reuptake inhibitors (SSRIs) (e.g., sertraline, fluvoxamine) may increase methadone plasma levels upon co-administration with METHADOSE and result in increased opioid effects and/or toxicity.
Co-administration of methadone with a serotonergic agent, such as a Selective Serotonin Re-uptake Inhibitor or a Serotonin Norepinephrine Re-uptake Inhibitor, may increase the risk of serotonin syndrome, a potentially life-threatening condition (see WARNINGS AND PRECAUTIONS).
Potentially Arrhythmogenic Agents: Methadone and QT Interval Prolongation:
In patients taking drugs affecting cardiac conduction, or drugs which may affect electrolyte balance, there is a risk of cardiac events when methadone is taken concurrently.
Extreme caution is necessary when any drug known to have the potential to prolong the QT interval is prescribed in conjunction with METHADOSE. Pharmacodynamic interactions may occur with concomitant use of METHADOSE and potentially arrhythmogenic agents such as Class I and III anti-arrhythmics, some neuroleptics and tricyclic antidepressants, and calcium channel blockers.
Caution should also be exercised when prescribing METHADOSE concomitantly with drugs capable of inducing electrolyte disturbances (hypomagnesemia, hypokalemia) that may prolong the QT interval. These drugs include diuretics, laxatives, and, in rare cases, mineralocorticoid hormones.
Opioid Antagonists, Mixed Agonist/Antagonists, and Partial Agonists:
As with other µ-agonists, patients maintained on methadone may experience withdrawal symptoms when given opioid antagonists, mixed agonist/antagonists, and partial agonists. Examples of such agents are naloxone, naltrexone, pentazocine, nalbuphine, butorphanol, and buprenorphine.
Opioid Antagonists:
Naloxone and naltrexone antagonises the analgesic, CNS and respiratory depressant effects of methadone and can rapidly precipitate withdrawal symptoms (see OVERDOSAGE). Similarly buprenorphine and pentazocine may precipitate withdrawal symptoms.
pH of Urine:
Drugs that acidify or alkalinise the urine may have an effect on clearance of methadone as it is increased at acidic pH and decreased at alkaline pH.
Others:
Methadone may have an effect on other drugs as a consequence of reduced gastro-intestinal motility.
9.3 Drug-Behavioural Interactions
The concomitant use of alcohol should be avoided (see WARNINGS AND PRECAUTIONS).
METHADOSE may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery (see WARNINGS AND PRECAUTIONS).
9.4 Drug-Drug Interactions
Table 1 - Established or Potential Drug-Drug Interactions
| Proper name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Monoamine oxidase inhibitors | C | ↑Methadone | May also increase the risk of serotonin syndrome, a potentially life-threatening condition. |
| Selective serotonin re-uptake inhibitors | C | ↑Methadone | May increase methadone plasma levels upon co-administration with METHADOSE and result in increased opioid effects and/or toxicity. |
SSRIs, SNRIs, TCAs, MAOIs (including linezolide and methylene blue), triptans, other serotonergic drugs (e.g., lithium) and serotonin-precursors such as L-tryptophan | C, T | ↑Methadone | May also increase the risk of serotonin syndrome, a potentially life-threatening condition. |
| Alcohol and other CNS depressants | C | ↑Methadone | May increase the general depressant effects of methadone when used concomitantly. |
| Potentially arrhythmogenic agents | T, C | ↑Methadone | Extreme caution is necessary when any drug known to have the potential to prolong the QT interval is prescribed in conjunction with METHADOSE. Pharmacodynamic interactions may occur with concomitant use of METHADOSE and potentially arrhythmogenic agents such as Class I and III anti-arrhythmics, some neuroleptics and tricyclic antidepressants, and calcium channel blockers. Caution should also be exercised when prescribing METHADOSE concomitantly |
| Proper name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| with drugs capable of inducing electrolyte disturbances (hypomagnesemia, hypokalemia) that may prolong the QT interval. These drugs include diuretics, laxatives, and, in rare cases, mineralocorticoid hormones. | |||
| Abacavir, efavirenz, nelfinavir, nevirapine, ritonavir | CT, C | ↓Methadone | Co-administration of these anti-retroviral agents resulted in increased clearance or decreased plasma levels of methadone. Methadone-maintained patients beginning treatment with these anti-retroviral drugs should be monitored for evidence of withdrawal effects and methadone dose should be adjusted accordingly. |
| Lopinavir + ritonavir combination | T | ↓Methadone | Co-administration may result in increased clearance or decreased plasma levels of methadone. |
| Amprenavir | CT | ↓Methadone | Methadone blood concentrations are decreased by the administration of abacavir plus amprenavir. |
| Histamine H2 antagonists such as cimetidine | T | ↑Methadone | Can reduce the protein binding of methadone resulting in increased opioid action. |
| Delavirdine | T | ↑Methadone | Dosage of methadone may need to be decreased when co-administered with delavirdine. |
| Rifampicin | C | ↓Methadone | Reduced plasma levels and increased urinary excretion of methadone can occur with concurrent administration of rifampicin. Adjustment of the dose of methadone may be necessary. |
| Ciprofloxacin | C | ↑Methadone | Plasma levels of methadone may increase with concurrent administration of ciprofloxacin due to inhibition of CYP1A2 and CYP3A4. Concomitant use may lead to sedation, confusion and respiratory depression. |
| Erythromycin | T, C | ↑Methadone | Theoretically erythromycin may increase methadone levels due to decreased methadone metabolism. |
| Fluconazole | CT, C | ↑Methadone | May raise methadone levels, due to decreased methadone metabolism. |
| Ketoconazole | T | ↑Methadone | May raise methadone levels, due to decreased methadone metabolism. |
| Proper name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Voriconazole | CT, C | ↑Methadone | May raise methadone levels due to decreased methadone metabolism. |
| Phenytoin, Carbamazepine | C | ↓Methadone | Induces methadone metabolism with the risk of precipitating withdrawal syndrome. Adjustment of the dose of methadone should be considered. |
| Phenobarbital | T | ↓Methadone | Induces methadone metabolism with the risk of precipitating withdrawal syndrome. |
| Primidone | T | ↓Methadone | Induces methadone metabolism with the risk of precipitating withdrawal syndrome. |
| Domperidone and metoclopramide | T | ↑Methadone | May increase the speed of onset but not the extent of methadone absorption by reversing the delayed gastric emptying associated with opioids. Conversely, methadone may antagonise the effect of domperidone/metoclopramide on gastro-intestinal activity. |
| Methadone | T | ↓Ciprofloxacin | Reduced serum concentrations of ciprofloxacin may occur. |
| Methadone | C | ↓Didanosine ↓Stavudine | Experimental evidence demonstrated that methadone decreased the area under the concentration-time curve (AUC) and peak levels for didanosine and stavudine, with a more significant decrease for didanosine. Methadone disposition was not substantially altered. |
| Methadone | CT | ↑Zidovudine | Experimental evidence demonstrated that methadone increased the AUC of zidovudine which could result in toxic effects. |
| Methadone | C | ↑Desipramine | Plasma levels of desipramine have increased with concurrent methadone administration. |
| Methadone | T | ↓Domperidone and metoclopramide | Methadone may antagonise the effect of domperidone/metoclopramide on gastro-intestinal activity. |
| Methadone | T | ↓Mexiletine | Methadone delays the absorption of mexiletine. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Pharmacokinetic studies show that concomitant grapefruit can cause a modest increase in methadone plasma levels. The clinical relevance of this is unknown.
9.6 Drug-Herb Interactions
St. John’s Wort
Administration of METHADOSE along with other CYP3A4 inducers may result in withdrawal symptoms.
9.7 Drug-Laboratory Test Interactions
Pregnancy Tests
Methadone may interfere with urine testing for pregnancy.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Methadone is an opioid agonist with actions predominantly at the µ receptor. The analgesic activity of the racemate is almost entirely due to the l-isomer, which is at least 10 times more potent as an analgesic than the d-isomer. The d-isomer lacks significant respiratory depressant activity but does have antitussive effects. Methadone also has some agonist actions at the κ and σ opioid receptors. These actions result in analgesia, depression of respiration, suppression of cough, nausea and vomiting (via an effect on the chemoreceptor trigger zone) and constipation. An effect on the nucleus of the oculomotor nerve, and perhaps on opioid receptors in the pupillary muscles causes pupillary constriction. All these effects are reversible by naloxone with a pA2 value similar to its antagonism of morphine. Like many basic drugs, methadone enters mast cells and releases histamine by a non-immunological mechanism. Similar to morphine, both isomers are 5-HT(3) receptor antagonists, although l-methadone producing greater inhibition than d-methadone. Methadone causes a dependence syndrome of the morphine type. Cross-tolerance between morphine and methadone has been demonstrated, as steady-state plasma methadone concentrations required for effectiveness (C50%) were higher in abstinent rats previously dosed with morphine, as compared to controls.
Some data indicate that methadone acts as an antagonist at the N-methyl-D-aspartate (NMDA) receptor. The contribution of NMDA receptor antagonism to methadone’s efficacy is unknown. Other NMDA receptor antagonists have been shown to product neurotoxic effects in animals.
10.2 Pharmacodynamics
Prolongation of the QT interval associated with methadone can lead to potentially fatal ventricular arrhythmias and is caused by block of the rapid component of the cardiac delayed rectifier K(+) current (I(Kr)), which is encoded by hERG related gene. In vitro effects of methadone have been compared to heroin in human embryonic kidney cells expressing hERG currents, with methadone exhibiting 100-fold higher potency (IC50 4.8 µM) at inhibiting hERG than heroin (IC50 427 µM).
Central Nervous System:
Methadone produces respiratory depression by direct action on brain stem respiratory centres.
The respiratory depression involves both a reduction in the responsiveness of the brain stem centres to increases in CO2 tension and to electrical stimulation.
Methadone depresses the cough reflex by direct effect on the cough centre in the medulla. Antitussive effects may occur with doses lower than those usually required for analgesia.
Methadone causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings).
Gastrointestinal Tract and Other Smooth Muscle:
Methadone causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in gastric, biliary and pancreatic secretions, spasm of the sphincter of Oddi, and transient elevations in serum amylase.
Cardiovascular System:
Methadone may produce release of histamine with or without associated peripheral vasodilation. Manifestations of histamine release and/or peripheral vasodilatation may include pruritus, flushing, red eyes, hyperhidrosis and/or orthostatic hypotension.
Endocrine System:
Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin, and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes.
Immune System:
In vitro and animal studies indicate that opioids have a variety of effects on immune functions, depending on the context in which they are used. The clinical significance of these findings is unknown.
10.3 Pharmacokinetics
Absorption
Methadone is one of the more lipid soluble opioids, and is well absorbed from the gastrointestinal tract. Following oral administration, the bioavailability of methadone ranges between 36 to 100% and peak plasma concentrations are achieved between 1 and 7.5 hours. Dose proportionality of methadone pharmacokinetics is not known. However, after administration of daily oral doses ranging from 10 to 225 mg, the steady-state plasma concentrations ranged between 65 to 630 ng/mL and the peak concentrations ranged between 124 to 1255 ng/mL. Effect of food on the bioavailability of methadone has not been evaluated.
Distribution
Methadone undergoes fairly extensive first pass metabolism. It is bound to albumin and other plasma proteins and to tissue proteins (probably lipoproteins), the concentrations in lung, liver and kidneys being much higher than in the blood. Methadone is unusual in the opioid class, in that there is extensive binding to tissue proteins and fairly slow transfer between some parts of this tissue reservoir and the plasma. Methadone is a lipophilic drug and the steady-state volume of distribution ranges between 1.0 to 8.0 L/kg. In plasma, methadone is predominantly bound to a1-acid glycoprotein (85% to 90%). Marked variations in plasma levels occur in dependent persons on a stable dose of oral methadone, without any relation to symptoms. Methadone is secreted in saliva, sweat, breast milk, amniotic fluid and umbilical cord plasma. The concentration in cord blood is about half the maternal levels.
Metabolism
Methadone is primarily metabolized by N-demethylation to an inactive metabolite, 2-ethylidene-1,5-dimethyl-3,3-diphenylpyrrolidene (EDDP). Cytochrome P450 enzymes, primarily CYP3A4, CYP2B6, CYP2C19, and to a lesser extent CYP2C9 and CYP2D6, are responsible for conversion of methadone to EDDP and other inactive metabolites, which are excreted mainly in the urine.
Elimination
The elimination of methadone is mediated by extensive biotransformation, followed by renal and fecal excretion. Published reports indicate that after multiple dose administration the apparent plasma clearance of methadone ranged between 1.4 and 126 L/h, and the terminal half-life (T½) was highly variable and ranged between 8 and 59 hours in different studies. Since methadone is lipophilic, it has been known to persist in the liver and other tissues. The slow release from the liver and other tissues may prolong the duration of methadone action despite low plasma concentrations.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of METHADOSE has not been evaluated in the pediatric population. Individuals under 18 years of age should not take METHADOSE.
- Geriatrics: The pharmacokinetics of METHADOSE has not been evaluated in the geriatric population.
- Gender: The pharmacokinetics of METHADOSE has not been evaluated for gender specificity.
- Race: The pharmacokinetics of METHADOSE has not been evaluated for race specificity.
- Hepatic Impairment: Methadone has not been extensively evaluated in patients with hepatic insufficiency. Methadone is metabolized by hepatic pathways, therefore patients with liver impairment may be at risk of accumulating methadone after multiple dosing (see also WARNINGS AND PRECAUTIONS, Special Populations).
Renal Impairment: Methadone pharmacokinetics has not been extensively evaluated in patients with renal insufficiency. Unmetabolized methadone and its metabolites are
- excreted in urine to a variable degree. Methadone is a basic (pKa=9.2) compound and the pH of the urinary tract can alter its disposition in plasma. Urine acidification has been shown to increase renal elimination of methadone. Forced diuresis, peritoneal dialysis, hemodialysis, or charcoal hemoperfusion have not been established as beneficial for increasing the elimination of methadone or its metabolites.
Pregnancy: The disposition of oral methadone has been studied in approximately 30 pregnant patients in the second and third trimesters. Elimination of methadone was significantly changed in pregnancy. Total body clearance of methadone was increased in pregnant patients compared to the same patients postpartum or to non-pregnant opioid-dependent women. The terminal half-life of methadone is decreased during second and third trimesters. The decrease in plasma half-life and increased clearance of methadone resulting in lower methadone trough levels during pregnancy can lead to withdrawal symptoms in some pregnant patients. The dosage may need to be increased or the dosing interval decreased in pregnant patients receiving methadone (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women and DOSAGE AND ADMINISTRATION).
Pregnant women appear to have significantly lower trough plasma methadone concentrations, increased plasma methadone clearance, and shorter methadone half-life than after delivery. Dosage adjustment using higher doses or administering the daily dose in divided doses may be necessary in pregnant women treated with METHADOSE (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION).
Teratogenic Effects – Methadone should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. There are no controlled studies of methadone use in pregnant women that can be used to establish safety. However, an expert review of published data on experiences with methadone use during pregnancy by the Teratogen Information System (TERIS) concluded that maternal use of methadone during pregnancy as part of a supervised, therapeutic regimen is unlikely to pose a substantial teratogenic risk (quantity and quality of data assessed as “limited to fair”). However, the data are insufficient to state that there is no risk (TERIS, last reviewed October, 2002).
Pregnant women involved in methadone maintenance programs have been reported to have significantly improved prenatal care leading to significantly reduced incidence of obstetric and fetal complications and neonatal morbidity and mortality when compared to women using illicit drugs. Several factors complicate the interpretation of investigations of the children of women who take methadone during pregnancy. These include the maternal adjunct use of illicit drugs, other maternal factors such as nutrition, infection, and psychosocial circumstances, limited information regarding dose and duration of methadone use during pregnancy, and the fact that most maternal exposure appears to occur after the first trimester of pregnancy. Reported studies have generally compared the risk of methadone to the risk of untreated addiction to illicit drugs or to addiction-free pregnancies.
- Drug Interactions (see DRUG INTERACTIONS, Drug Interactions Overview): Methadone undergoes hepatic N-demethylation by cytochrome P450 isoforms, principally CYP3A4, CYP2B6, CYP2C19, and to a lesser extent by CYP2C9 and CYP2D6. Co-administration of methadone with inducers of these enzymes may result in more rapid methadone metabolism, and potentially, decreased effects of methadone. Conversely, administration with CYP inhibitors may reduce metabolism and potentiate methadone’s effects. Pharmacokinetics of methadone may be unpredictable when co-administered with drugs that are known to both induce and inhibit CYP enzymes. Although anti-retroviral drugs such as efavirenz, nelfinavir, nevirapine, ritonavir, lopinavir + ritonavir combination are known to inhibit some CYPs, they are shown to reduce the plasma levels of methadone, possibly due to their CYP induction activity. Therefore, drugs administered concomitantly with methadone should be evaluated for interaction potential; clinicians are advised to evaluate individual response to drug therapy before making a dosage adjustment.
11 STORAGE, STABILITY AND DISPOSAL
Dispense in tight containers, protected from light. Store at room temperature (15°C to 30°C). Keep out of reach and sight of children.
METHADOSE should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended. Unused or expired METHADOSE should be properly disposed of as soon as it is no longer needed to prevent accidental exposure to others, including children or pets. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
12 SPECIAL HANDLING INSTRUCTIONS
Dispense in tight containers, protected from light.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Methadone Hydrochloride
Chemical name: 6-(dimethylamino)-4,4-diphenylheptan-3-one hydrochloride
Molecular formula and molecular mass: C21H27NO . HCl, 345.91
Structural formula:
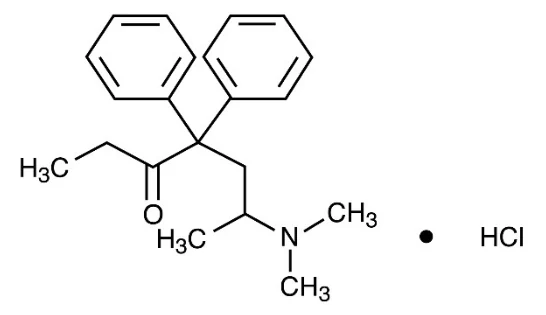
Physicochemical properties:
Methadone hydrochloride is a white, essentially odorless, bitter-tasting crystalline powder. It is very soluble in water, soluble in isopropanol and in chloroform, and practically insoluble in ether and in glycerine. It is present in METHADOSE as the racemic mixture. Methadone hydrochloride has a melting point of 235°C, a pKa of 8.25 in water at 20°C, a solution (1 part per 100) pH between 4.5 and 6.5, a partition coefficient of 117 at pH 7.4 in octanol/wat.
Other ingredients of METHADOSE Oral Concentrate: artificial cherry flavor, citric acid anhydrous, FD&C Red No. 40, D&C Red No. 33, methylparaben, poloxamer 407, propylene glycol, propylparaben, purified water, sodium citrate dihydrate, sucrose.
Other ingredients of METHADOSE Sugar-Free Oral Concentrate: citric acid anhydrous, purified water, sodium benzoate.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
In animals, methadone is 3 to 10 times more toxic than morphine, depending on the species, and 2 to 3 times more toxic than meperidine. In acute dose toxicity studies in rats, methadone is about 10 times more toxic than morphine orally, about 6 times more toxic subcutaneously, and about 25 times more toxic intravenously. The l-isomer of methadone, which predominantly accounts for withdrawal suppression activity of the racemic mixture, demonstrates a similar toxicity to that seen with d-l-methadone.
The following table summarizes the acute toxicity data for d-l-methadone obtained in rats and mice.
| Route | LD50 Values (mg/kg) | |
| Mouse | Rat | |
| po | 95 | 86 |
| ip | 31 | 18 |
| sc | 27 | 30 |
| iv | 24 | 11 |
Four of 6 monkeys (stumped tail macaques) orally administered methadone at a dose of 5 mg/kg three times per day (total daily dose 15 mg/kg) for two or more weeks developed sudden toxicity. In general, toxicity was associated with plasma methadone concentrations greater than 130 ng/mL (range 130 – 420 ng/mL) and in each case occurring after the first morning dose. Findings included respiratory depression, respiratory arrest resulting in death (1 monkey), shallow breathing, ataxia, fixed gaze, and EEG changes including attenuated visual evoked response waves. Two monkeys not developing toxicity had plasma methadone levels ranging from 20 to 123 ng/mL.
Morphine has been shown to elevate corticosterone and suppress the immune system. Methadone and morphine treatment in mice resulted in suppression of hepatic and splenic phagocytosis. However, immune response to parasitic, bacterial and yeast infections following methadone treatment was intact and, unlike morphine, phagocytosis by peripheral leukocytes and monocytes and alveolar macrophages was not altered. Chronic exposure to morphine and methadone produced tolerance and normal function in human cultured monocyte-derived macrophages, while withdrawal decreased phagocytic function in a similar manner to acute opioid exposure. Phagocytic activity in liver macrophages (Kupffer cells) from female mice dosed with 30 mg/kg methadone every 6 hours for 5 days, was decreased up to 59% and changes were dose-dependent. There was also a significant decrease in the ability of resident splenic macrophages to phagocytize RBCs. However these immunologic changes did not affect host resistance to bacteria.
Carcinogenicity:
The results of carcinogenicity assessment in B6C2F1 mice and Fischer 344 rats following dietary administration of two doses of methadone hydrochloride have been published. Mice consumed 15 mg/kg/day or 60 mg/kg/day methadone for two years. These doses were approximately 0.6 and 2.5 times a human daily oral dose of 120 mg/day on a body surface area basis (mg/m2). There was a significant increase in pituitary adenomas in female mice treated with 15 mg/kg/day but not with 60 mg/kg/day. Under the conditions of the assay, there was no clear evidence for a treatment-related increase in the incidence of neoplasms in male rats. Due to decreased food consumption in males at the high dose, male rats consumed 16 mg/kg/day and 28 mg/kg/day of methadone for two years. These doses were approximately 1.3 and 2.3 times a human daily oral dose of 120 mg/day, based on body surface area comparison. In contrast, female rats consumed 46 mg/kg/day or 88 mg/kg/day for two years. These doses were approximately 3.7 and 7.1 times a human daily oral dose of 120 mg/day, based on body surface area comparison. Under the conditions of the assay, there was no clear evidence for a treatment-related increase in the incidence of neoplasms in either male or female rats.
Genotoxicity:
There are several published reports on the potential genetic toxicity of methadone. Methadone tested negative in tests for chromosome breakage and disjunction and sex-linked recessive lethal gene mutations in germ cells of Drosophila using feeding and injection procedures. In contrast, methadone tested positive in the in vivo mouse dominant lethal assay and the in vivo mammalian spermatogonial chromosome aberration test. Additionally, methadone tested positive in the E.coli DNA repair system and Neurospora crassa and mouse lymphoma forward mutation assays.
Reproductive and Developmental Toxicology:
Reproductive studies in rats revealed no evidence of teratogenicity. Multi-generational reproductive toxicity studies in male and female rats showed decreased body weight and number of pups (F1) and increased mortality (F2) with no changes in the F3 generation. Subcutaneous doses of 20 to 28 mg/kg/day from gestation days 6 through 15 in CD-1 mice resulted in increased resorptions and decreased live births per litter as well as affecting fetal ossification of digits, sternum and skull. Acute methadone dosing in male rats has been shown to increase the frequency of neonatal deaths. However, after chronic dosing, male rats showed no dominant lethal effect and spermatogenesis was not affected. Effects on the male reproductive system between rodent species show conflicting results. Methadone doses of 4 to 6 mg/kg/day for 3 days affected spermatogenesis in male mice. Germ cell chromosomal aberrations occurred in a dose-dependent manner and there were increased numbers of preimplantation deaths.
Published animal data have reported increased neonatal mortality in the offspring of male rats that were treated with methadone prior to mating. In these studies, the female rats were not treated with methadone, indicating paternally-mediated developmental toxicity. Specifically, methadone administered to the male rat prior to mating with methadone-naïve females resulted in decreased weight gain in progeny after weaning. The male progeny demonstrated reduced thymus weights, whereas the female progeny demonstrated increased adrenal weights. Furthermore, behavioral testing of these male and female progeny revealed significant differences in behavioral tests compared to control animals, suggesting that paternal methadone exposure can produce physiological and behavioral changes in progeny in this model.
Other animal studies have reported that perinatal exposure to opioids including methadone alters neuronal development and behavior in the offspring. Perinatal methadone exposure in rats has been linked to alterations in learning ability, motor activity, thermal regulation, nociceptive responses and sensitivity to drugs. Additional animal data demonstrates evidence for neurochemical changes in the brains of methadone-treated offspring, including changes to the cholinergic, dopaminergic, noradrenergic and serotonergic systems. Additional studies demonstrated that methadone treatment of male rats for 21 to 32 days prior to mating with methadone-naïve females did not produce any adverse effects, suggesting that prolonged methadone treatment of the male rat resulted in tolerance to the developmental toxicities noted in the progeny. Mechanistic studies in this rat model suggest that the developmental effects of “paternal” methadone on the progeny appear to be due to decreased testosterone production. These animal data mirror the reported clinical findings of decreased testosterone levels in human males on methadone maintenance therapy for opioid addiction and in males receiving chronic intraspinal opioids.
Maternal exposure (5 mg/kg) of rats to d-l-methadone during gestation or lactation resulted in perinatal exposure in pups that produced reduced body weight, body length, head diameter and organ weights. Perinatal methadone treatment in rats results in dependence, developmental delays, and affects brain growth and development in their offspring. Chronic administration of methadone in pregnant Cynomolgus monkeys significantly reduced birth weight. In the guinea pig, prenatal methadone treatment resulted in decreased body weight and withdrawal symptoms in offspring. Morphine and methadone were associated with respiratory changes in guinea pig pups with the effect of morphine being more prolonged.
Methadone does not appear to be teratogenic in the rat or rabbit models. However, following large doses, methadone produced teratogenic effects in the guinea pig, hamster and mouse. One published study in pregnant hamsters indicated that a single subcutaneous dose of methadone ranging from 31 to 185 mg/kg (the 31 mg/kg dose is approximately twice a human daily oral dose of 120 mg/day on a mg/m2 basis) on Day 8 of gestation resulted in a decrease in the number of fetuses per litter and an increase in the percentage of fetuses exhibiting congenital malformations described as exencephaly, cranioschisis, and “various other lesions.” The majority of the doses tested also resulted in maternal death. In another study, a single subcutaneous dose of 22 to 24 mg/kg methadone (estimated exposure was approximately equivalent to a human daily oral dose of 120 mg/day on a mg/m2 basis) administered on Day 9 of gestation in mice also produced exencephaly in 11% of the embryos. However, no effects were reported in rats and rabbits at oral doses up to 40 mg/kg (estimated exposure was approximately 3 and 6 times, respectively, a human daily oral dose of 120 mg/day on a mg/m2 basis) administered during days 6-15 and 6-18, respectively.