


Product Monograph - Mylan-Acebutolol
Action and Clinical Pharmacology
Acebutolol Hydrochloride is a β-adrenergic receptor-blocking agent. In vitro and in vivo animal studies show it has a preferential effect on beta1 adrenoreceptors, chiefly located in cardiac muscle. This preferential effect is not absolute, however, and at higher doses, Acebutolol
Hydrochloride inhibits beta2 adrenoreceptors, chiefly located in the bronchial and vascular musculature. It possesses some partial agonist activity (or intrinsic sympathomimetic activity -
ISA). It is used in the treatment of hypertension and/or prophylaxis of angina pectoris.
The mechanism of the antihypertensive effect has not been established. Among the factors that may be involved are:
- a) competitive ability to antagonize catecholamine-induced tachycardia at the ~3-receptor sites in the heart, thus decreasing cardiac output;
- b) inhibition of renin release by the kidneys;
- c) inhibition of the vasomotor centres.
The mechanism of the anti-anginal effect is also uncertain. An important factor may be the reduction of myocardial oxygen requirements by blocking catecholamine-induced increases in heart rate, systolic blood pressure, and the velocity and extent of myocardial contraction.
Acebutolol Hydrochloride is well absorbed from the gastrointestinal tract. It undergoes extensive first pass hepatic biotransformation, with an absolute bioavailability of approximately 40% for the parent compound. The major metabolite, an N-acetyl derivative (diacetolol), is pharmacologically active. This metabolite is equipotent to Acebutolol Hydrochloride and, in cats, is more cardioselective than Acebutolol Hydrochloride; therefore, this first-pass phenomenon does not attenuate the therapeutic effect of Acebutolol Hydrochloride. Food intake does not have a significant effect on the area under the plasma concentration time curve [AUC]
of Acebutolol Hydrochloride although the rate of absorption and peak concentration decreases slightly.
The plasma elimination half-life of Acebutolol Hydrochloride is approximately 3 to 4 hours, while that of its metabolite, diacetolol, is 8 to 13 hours. The time to reach peak concentration for
Acebutolol Hydrochloride is 2.5 hours and for diacetolol, after oral administration of Acebutolol
Hydrochloride, 3.5 hours.
Within the single oral dose range of 200 to 400 mg, the kinetics are dose proportional. However, this linearity is not seen at higher doses, probably due to saturation of hepatic biotransformation sites. In addition, after multiple dosing the lack of linearity is also seen by AUC increases of
approximately 100% as compared to single oral dosing. Elimination via renal excretion is approximately 30% to 40% and by non-renal mechanisms 50% to 60%, which includes excretion into the bile and direct passage through the intestinal wall.
Acebutolol Hydrochloride has a low binding affinity for plasma proteins (about 26%).
Acebutolol Hydrochloride and its metabolite, diacetolol, are relatively hydrophilic and therefore only minimal quantities have been detected in the cerebrospinal fluid (CSF).
The bioavailability study was performed on healthy volunteers using MYLAN-ACEBUTOLOL
(Acebutolol Hydrochloride) 400 mg tablets. The rate and extent of absorption of the parent compound acebutolol after a single dose of 400 mg MYLAN-ACEBUTOLOL and the marketed brand were measured and compared. The pharmacokinetic data are presented in the table below:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
MYLAN-ACEBUTOLOL
(1 X 400 mg)
From measured data
| Geometric Mean Arithmetic Mean (C.V. %) | |||
| PARAMETER | MYLAN- ACEBUTOLOL 400 mg tablets (Mylan Pharmaceuticals ULC) (L) NL095 | MONITAN® 400 mg tablets (Wyeth Ayerst, Canada) (L) ICMN-A5 | RATIO OF GEOMETRIC MEANS % |
| AUCT (ng. hr/mL) | 3935.47 4069.3 (29.4 %) | 3744.29 3873.0 (26.2 %) | 105.1 % |
| AUCf (ng. hr/mL) | 4103.63 4236.0 (28.7 %) | 3917.29 4053.2 (26.8 %) | 104.8 % |
| Cmax (ng /mL) | 921.616 1007.45 (58.1 %) | 795.912 858.63 (36.8 %) | 115.8% |
| Tmax (h) | 2.227(35.8%) | 2.409(31.8%) | N/A |
| T1/2 (h) | 4.083 (34.1 %) | 4.276 (39.2 %) | N/A |
for Tmax and T1/2 arithmetic mean (C.V. %) are presented
Indications and Clinical Use
- a)
HYPERTENSION: MYLAN-ACEBUTOLOL (Acebutolol Hydrochloride) is indicated in patients with mild to moderate hypertension. It is usually used in combination with other drugs, particularly a thiazide diuretic. However, it may be tried alone as an initial agent in those patients in whom, in the judgment of the physician, treatment should be started with a
β-blocker rather than a diuretic.
In patients with severe hypertension a β-adrenergic blocking agent may be used as part of a multiple drug regimen, which would normally include a diuretic and a vasodilator.
The combination of Acebutolol Hydrochloride with a diuretic or peripheral vasodilator has been found to be compatible and generally more effective than Acebutolol Hydrochloride alone. Limited experience with other antihypertensive agents has not shown evidence of incompatibility.
MYLAN-ACEBUTOLOL is not indicated in the emergency treatment of hypertensive crises.
- b) ANGINA PECTORIS: MYLAN-ACEBUTOLOL is indicated in the long-term management of patients with angina pectoris due to ischemic heart disease.
Contraindications
MYLAN-ACEBUTOLOL (Acebutolol Hydrochloride) should not be used in the presence of:
- 1) sinus bradycardia,
- 2) second and third degree A-V block,
- 3) right ventricular failure secondary to pulmonary hypertension,
- 4) congestive heart failure,
- 5) cardiogenic shock,
- 6) anaesthesia with agents that produce myocardial depression, e.g. ether.
Warnings
- a)
Increase in antinuclear antibody (ANA) titer was observed in approximately 12.5% of patients on chronic Acebutolol Hydrochloride therapy. Rare instances (<1%) of a syndrome resembling lupus erythematosus have been reported with maintenance Acebutolol
Hydrochloride therapy. Similar symptoms were occasionally observed with some other β-blockers. In addition to increased ANA titers, polyarthralgia, myalgia and pleuritic pain were the main presenting symptoms. Symptoms and ANA titers appear reversible upon discontinuation of Acebutolol Hydrochloride therapy. The drug should be withdrawn if
symptoms appear or if the results of ANA testing are significantly positive. Patients should be followed up both clinically and serologically until resolution of symptoms.
- b)
Cardiac Failure
Special caution should be exercised when administering MYLAN-ACEBUTOLOL
(Acebutolol Hydrochloride) to patients with a history of heart failure. Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure, and inhibition with β-blockade always carries the potential hazard of further depressing myocardial contractility and precipitating cardiac failure. MYLAN-ACEBUTOLOL acts selectively without abolishing the inotropic action of digitalis on the heart muscle. However, the positive inotropic action of digitalis may be reduced by the negative inotropic effect of
Acebutolol Hydrochloride when the two drugs are used concomitantly.
The effects of β-blockers and digitalis are additive in depressing A-V conduction.
In patients without a history of cardiac failure, continued depression of myocardium over a period of time can, in some cases, lead to cardiac failure. Therefore, at the first sign or symptom of impending cardiac failure, patients should be fully digitalised and/or given a diuretic and the response observed closely. If cardiac failure continues despite adequate digitalisation and diuretic therapy, MYLAN-ACEBUTOLOL therapy should be immediately withdrawn.
- c)
Abrupt cessation of therapy with MYLAN-ACEBUTOLOL
Patients with angina should be warned against abrupt discontinuation of MYLAN-
ACEBUTOLOL. There have been reports of severe exacerbation of angina, and of myocardial infarction or ventricular arrhythmias occurring in patients with angina pectoris, following abrupt discontinuation of β-blocker therapy. The last two complications may occur with or without preceding exacerbation of angina pectoris. Therefore, when discontinuation of MYLAN-ACEBUTOLOL is planned in patients with angina pectoris, the dosage should be gradually reduced over a period of about two weeks and the patient should be carefully observed. The same frequency of administration should be maintained. In situations of greater urgency, Acebutolol Hydrochloride therapy should be discontinued stepwise and under conditions of closer observation. If angina markedly worsens or acute coronary insufficiency develops, it is recommended that treatment with MYLAN-ACEBUTOLOL be reinstituted promptly, at least temporarily.
- d)
Various skin rashes and conjunctival xerosis have been reported with 13-blockers, including
Acebutolol Hydrochloride. A severe syndrome (oculo-muco-cutaneous syndrome) whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the chronic use of one 13-adrenergic-blocking agent (practolol). This syndrome has not been observed with Acebutolol Hydrochloride or any other such agent.
However, physicians should be alert to the possibility of such reactions and should discontinue treatment in the event that they occur.
- e) Severe sinus bradycardia may occur with the use of Acebutolol Hydrochloride from unopposed vagal activity remaining after blockade of beta1-adrenergic receptors; in such cases, dosage should be reduced.
- f)
In patients with thyrotoxicosis, the possible deleterious effects from long-term use of
Acebutolol Hydrochloride have not been adequately appraised. Acebutolol Hydrochloride may give a false impression of improvement by masking the clinical signs of continuing hyperthyroidism or its complications. Therefore, abrupt withdrawal of Acebutolol
Hydrochloride may be followed by an exacerbation of the symptoms of hyperthyroidism, including thyroid storm.
- g)
Use in Pregnancy
Reproduction studies have been performed with Acebutolol Hydrochloride in rats and rabbits at doses of up to 60 mg/kg/day by the oral route and 18 mg/kg/day by the I.V. route. In one rabbit study where Acebutolol Hydrochloride was administered by the I.V. route, the following malformations were observed: rib defects, gastroschisis, ventricular septal defect, dysplasia of urogenital system and umbilical hernia. These results could not be confirmed in a repeat intravenous study and were not seen in a study using the oral route.
Studies have also been performed with diacetolol (the major metabolite of Acebutolol
Hydrochloride in man) at doses of up to 450-mg/kg/day p.o. in rabbits and 1,800-mg/kg/day p.o. in rats. There was a significant elevation of postimplantation loss in rabbit dams
receiving 450 mg/kg/day, a level at which food consumption and body weight gain were reduced; a non-statistically significant increase in incidence of bilateral cataracts was also noticed in rat fetuses from dams treated with 1,800 mg/kg/day.
There has been no experience with the use of Acebutolol Hydrochloride in pregnant women;
however, studies have shown that both acebutolol and diacetolol cross the placenta.
Acebutolol Hydrochloride should not be given to pregnant patients. Its use in women with child bearing potential requires that the anticipated benefit be cautiously weighed against possible hazards.
- h) Lactation
Acebutolol and diacetolol appear in breast milk with a milk plasma ratio of 7.1 and 12.2 respectively. Use in nursing mothers is not recommended.
Precautions
- a)
Patients with bronchospastic disease should in general not receive a β-blocker. Because of its relative β1 selectivity, however, low doses of Acebutolol Hydrochloride may be used with caution in patients with bronchospastic disease who do not respond to, or who cannot tolerate, alternative treatment. Since β1 selectivity is not absolute and is dose-dependent, a β2 stimulating agent should be administered concomitantly and the lowest possible dose of
Acebutolol Hydrochloride should be used initially, preferably in divided doses to avoid the higher plasma levels associated with the longer dose-interval.
There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to pharmacological effects of beta-blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other, these doses can be associated with excessive alpha-adrenergic stimulation with consequent hypertension, reflux bradycardia and heart block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids and the use of beta agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm, and norepinephrine to overcome hypotension.
- b) Acebutolol Hydrochloride should be administered with caution to patients subject to spontaneous hypoglycemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. β-adrenergic blockers may mask the premonitory signs and symptoms of acute hypoglycemia.
- c)
Acebutolol Hydrochloride should be administered with caution to patients with impaired renal function. Acebutolol hydrochloride is excreted through the G.I. tract, but the active metabolite diacetolol, is eliminated predominantly by the kidney. There is a linear relationship between renal clearance of diacetolol and creatinine clearance. The daily dose of
Acebutolol Hydrochloride should be reduced in patients with a creatinine clearance less than
50 mL/min.
- d) Geriatrics: Acebutolol Hydrochloride has been used in the elderly without specific adjustment of dosage. However, this patient population may require lower maintenance doses because the bioavailability of both acebutolol hydrochloride and its metabolite are approximately doubled in this age group. This increased bioavailability is probably due to decreases in first-pass metabolism and renal function in the elderly.
- e) Acebutolol Hydrochloride dosage should be individually adjusted when used concomitantly with other antihypertensive agents (see Dosage and Administration).
- f) Liver function tests should be performed at regular intervals during long-term treatment.
- g)
Elective or emergency surgery: The management of patients being treated with 13-blockers and undergoing elective or emergency surgery is controversial.
Although β-adrenergic-receptor blockade impairs the ability of the heart to respond to β-adrenergically-mediated reflex stimuli, abrupt discontinuation of therapy with Acebutolol
Hydrochloride may be followed by severe complications (see WARNINGS). Some patients receiving β-adrenergic-blocking agents have been subject to protracted severe hypotension during anaesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported. For these reasons, in patients with angina undergoing elective surgery, Acebutolol
Hydrochloride should be withdrawn gradually following the recommendation given under
Abrupt Cessation of Therapy (see WARNINGS). According to available evidence, all
clinical and physiological effects of β-blockade are no longer present 72 hours after cessation of medication.
In emergency surgery, since Acebutolol Hydrochloride is a competitive inhibitor of β-adrenergic-receptor agonists, its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol.
- h) Usage in children: There is no experience with Acebutolol Hydrochloride in the treatment of pediatric age groups and therefore use in children is not recommended.
- i)
Drug interactions: Catecholamine-depleting drugs, such as reserpine, may have an additive effect when given with β-blocking agents. Patients treated with Acebutolol Hydrochloride plus catecholamine depletors should therefore be observed closely for evidence or marked bradycardia or hypotension which may be present as vertigo, syncope/pre-syncope, or orthostatic changes in blood pressure without compensatory tachycardia.
Exaggerated hypertensive responses have been reported from the combined use of β-adrenergic antagonists and α-adrenergic stimulants, including those contained in proprietary cold remedies and vasoconstrictive nasal drops. Patients receiving β-blockers should be warned of this potential hazard.
No significant interactions of Acebutolol Hydrochloride with digoxin, hydrochlorothiazide, hydralazine, sulfinpyrazone, oral contraceptives, tolbutamide or warfarin have been observed.
Should it be decided to discontinue therapy in patients receiving β-blockers and clonidine concurrently, the β -blocker should be discontinued several days before the gradual withdrawal of clonidine. It has been suggested that withdrawal of clonidine in the presence of
β-blockade may exaggerate the clonidine withdrawal syndrome (see also Prescribing
Information for clonidine).
Adverse Reactions
The incidence of treatment-related side effects is derived from clinical trials in 3,090 patients with hypertension, angina pectoris or arrhythmia.
The most serious adverse reactions encountered with Acebutolol Hydrochloride are congestive heart failure, severe bradycardia and bronchospasm occurring in less than 1% of patients.
The most common adverse reactions reported are fatigue (4%), dyspnea (2.5%), nausea (2%), dizziness (2%), hypotension (1%) and rashes (1%).
Adverse reactions grouped by organ system are as follows:
Cardiovascular
- Congestive heart failure (see Warnings)
- Secondary effects of decreased cardiac output, which include: syncope, vertigo, lightheadedness and postural hypotension
- Severe bradycardia
- Lengthening of PR interval
- Second and third degree A-V block
- Sinus arrest
- Palpitation
- Chest pain
- Cold extremities
- Raynaud’s phenomenon
- Hot flushes
- Pain in legs
- Edema
Central Nervous System
- Headache
- Dizziness
- Mental depression
- Tiredness
- Drowsiness or somnolence
- Light-headedness
- Anxiety
- Tinnitus
- Weakness
- Confusion
- Vivid dreams
- Paresthesia
- Insomnia
Gastrointestinal
- Nausea and vomiting
- Heartburn
- Indigestion
- Flatulence
- Abdominal pain
- Diarrhea
- Constipation
Respiratory
- Dyspnea
- Cough
- Shortness of breath
- Wheezing
- Bronchospasm
Allergic-Dermatological (see Warnings)
- Urticaria
- Pruritus
- Sweating
- Exfoliative dermatitis
- Psoriasiform rash
- Lupus-like syndrome with arthralgia, myalgia, dyspnea and pleuritic pain, reversible upon cessation of the drug
EENT
- Blurred vision and non-specific visual disturbances
- Itching eyes
- Conjunctivitis
Miscellaneous
- Weight gain
- Loss of appetite
- Decrease in libido
- Shivering
- Micturition (frequency)
- Nocturia
Laboratory tests
Occasional reports of increased transaminase, alkaline phosphatase and lactic dehydrogenase values.
Positive antinuclear antibodies (see Warnings).
Symptoms and Treatment of Overdosage
Symptoms of Overdosage: The most common signs to be expected with β-adrenergic blocking agent are bradycardia, congestive heart failure, hypotension, bronchospasm and hypoglycemia.
Treatment of Overdosage: If overdosage occurs, in all cases therapy with Acebutolol
Hydrochloride should be discontinued and the patient observed closely. In addition, if required, the following therapeutic measures are suggested:
- 1. Bradycardia: atropine or another anticholinergic drug.
- 2. Heart block (second or third degree): isoproterenol or transvenous cardiac pacemaker.
- 3. Congestive heart failure: conventional therapy.
- 4. Hypotension (depending on associated factors): epinephrine rather than isoproterenol or norepinephrine may be useful in addition to atropine and digitalis [see Precaution concerning the use of epinephrine in β-blocked patients].
- 5. Bronchospasm: aminophylline or isoproterenol.
- 6. Hypoglycemia: intravenous glucose.
Acebutolol Hydrochloride and its major metabolite are dialyzable.
It should be remembered that Acebutolol Hydrochloride is a competitive antagonist of isoproterenol and hence large doses of isoproterenol can be expected to reverse many of the effects of excessive doses of Acebutolol Hydrochloride. However, the complications of excess isoproterenol should not be overlooked.
Dosage and Administration
The dose of Acebutolol Hydrochloride must always be adjusted to the individual requirements of the patient in accordance with the following guidelines:
Hypertension:
Acebutolol Hydrochloride is usually used in conjunction with other anti-hypertensive agents, particularly thiazide diuretics but may be used alone (see Indications).
Acebutolol Hydrochloride treatment should be initiated with doses of 100 mg twice daily. If an adequate response is not seen after one week, the dosage should be increased to 200 mg twice daily. In some cases, the daily dosage may need further increments of 100 mg twice daily at intervals of not less than two weeks, up to the maximum of 400 mg twice daily.
The maintenance dose is within the range of 400 to 800 mg daily. Patients who show a satisfactory response at a daily dose of 400 mg or less may be given the total dose once daily in the morning. Daily doses above this should be divided into two equal doses.
Angina Pectoris:
The initial dose is 200 mg twice daily. If after two weeks a satisfactory response has not been obtained, the dosage should be increased to a maximum of 300 mg twice daily.
The usual maintenance dose of Acebutolol Hydrochloride in angina pectoris is in the range of
200 to 600 mg daily administered in two divided doses.
In patients adequately controlled on 400 mg daily, a lower maintenance dose of 100 mg twice a day may be tried.
Use in the Elderly:
Older patients have an approximately 2-fold increase in bioavailability and are likely to require lower maintenance doses.
Use in Patients with impaired Renal Function:
The daily dose of Acebutolol Hydrochloride should be reduced by 50% when creatinine clearance is less than 50 mL/min and by 75% when it is less than 25 mL/min (see Precautions).
Acebutolol Hydrochloride and its metabolite are dialyzable.
Pharmaceutical Information
Drug Substance
Proper Name Acebutolol Hydrochloride
Chemical Name (RS)N- [3 -acetyl-4- [2-hydroxy-3 -[(1-methyl-
ethyl)amino]propoxy]phenyl] -butanamide hydrochloride
Chemical Formula C18H28N2O4 · HCL
Structural Formula
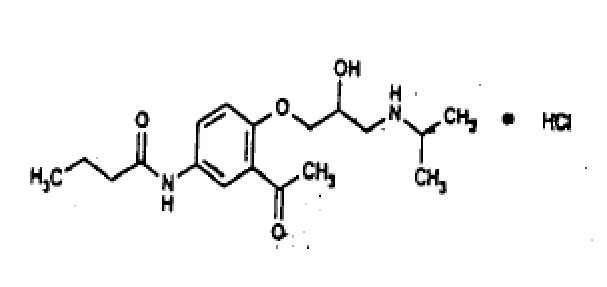
and enantiomer
Molecular Weight 372.89
Physical Form White to slightly yellow crystalline powder; odourless and tasteless.
Solubility It is freely soluble in water.
pKa value 9.46 (0.3 g in a mixture of 60 mL of water and 10 mL of ethanol)
Melting Range 141-145°C.
Composition (Non-medicinal Ingredients):
Each tablet contains: Maize Starch, Povidone K 30, Purified Water, Microcrystalline Cellulose,
Talc, Colloidal Anhydrous Silica, Magnesium Stearate, Opadry White OY-LS-28908*.
* The coating material contains: Titanium Dioxide, Lactose, H.P.M.C. 2910 l5cP, Polyethylene
Glycol 4000, H.P.M.C. 2910 3cP, H.P.M.C. 2910 50cP.
Stability and Storage Recommendations
Store at 15 - 30°C. Protect from light.
Availability of Dosage Forms
MYLAN-ACEBUTOLOL 100 mg, normal convex round, film coated white tablets, debossed “AC/100” on one side and “G” on the other. Available in bottles of 100 and 500.
MYLAN-ACEBUTOLOL 200 mg, normal convex oval film coated white tablets, debossed “AC/200” on one side and “G” on the other. Available in bottles of 100 and 500.
MYLAN-ACEBUTOLOL 400 mg, normal convex oblong, film coated white tablets, debossed “AC/400” on one side and “G” on the other. Available in bottles of 100.
Pharmacology
Effect on the Cardiovascular System
Administration of acebutolol hydrochloride to the cat and the dog has shown that low doses block isoproterenol-induced tachycardia (chronotropic action). Higher doses are required to
block isoproterenol-induced hypotension. Similar findings were seen in anaesthetized cat and guinea pig. Doses of 5 mg intravenously and 100 mg orally blocked isoproterenol-induced tachycardia in man. The action or isoproterenol on the FEV was not changed. A dose-related inhibition of reflex tachycardia to passive tilting and to nitroglycerin-induced tachycardia was observed. Acebutolol hydrochloride markedly lowered exercise-induced hypertension and tachycardia.
In the anaesthetized dog, high doses (10-20 mg/kg) of acebutolol hydrochloride infused slowly resulted in an increased PR interval and a decreased dP/dt.
In man, oral or intravenous acebutolol hydrochloride usually caused a dose-related reduction in heart rate, cardiac index, dP/dt (left ventricular contractility) and cardiac output. Little or no effect was produced on blood pressure, peripheral vascular resistance or pulmonary functions
(FEV and FVC).
Acebutolol hydrochloride, in low doses (0.05 - 0.5 mg/kg) controls sympathetically-induced arrhythmias in several species. High intravenous and oral doses are effective in ouabain-induced arrhythmias (anaesthetized dog and conscious rabbit). Ventricular arrhythmias in dogs with coronary ligation are reduced by acebutolol hydrochloride.
Electrophysiological studies in man showed delayed AV conduction time and increased refractoriness of the AV node without significantly affecting sinus node recovery time, a trial refractory period, or the HV conduction time.
Membrane stabilizing properties have been shown in three animal models. However, this effect of acebutolol hydrochloride is not manifested at the doses used clinically.
ISA was demonstrated in catecholamine-depleted rats by tachycardia induced by intravenous administration of the drug.
Effect on Pulmonary Function
The effects on airway resistance (FEV and FVC) of single oral doses of 100 and 200 mg of acebutolol hydrochloride were assessed in 15 patients with bronchial asthma. Peak flow was measured in 9 of these patients. No bronchodilator was used.
The drug did not have a significant effect on any of the pulmonary function tests. Clinically, one subject developed bronchospasm on the 100 mg dose but not on the 200 mg.
In another study, 300 mg single doses were given to 10 patients with bronchial asthma. No bronchodilator was used. There was no significant difference on FEV, but specific airway conductance (SC AW) was reduced. When isoproterenol was subsequently administered, the bronchodilator response (rise in FEV1) was also decreased.
Effect on Plasma Renin
Acebutolol hydrochloride caused a significant decrease in plasma renin in hypertensive patients.
This decrease was closely correlated to the decrease in blood pressure.
Effect on Lipolysis and Glucogenolysis
In healthy volunteers, acebutolol hydrochloride did not affect serum glucose, triglycerides or cholesterol. The release of free fatty acids following the administration of isoproterenol was inhibited. The drug potentiated the initial insulin-induced hypoglycemia but did not delay the return of normoglycemia.
Toxicology
Acute toxicity
| SPECIES | SEX | ROUTE | LD5O (mg/mL) | FINDINGS |
| Mice | F | I.V. | 78 | Sedation, convulsion, respiratory depression. |
| M | I.V. | 75 | ||
| F | P.O. | > 2,610 | ||
| M | P.O. | > 2,250 | ||
| Rats | F | I.V. | 120 | Sedation, ataxia, respiratory depression. |
| M | I.V. | 115 | ||
| F | P.O. | 5,200 | ||
| M | P.O. | 3,200 | ||
| Dogs | M/F | I.V. | > 40 to < 63 | Retching and vomiting, ataxia, weak pulse, respiratory depression. |
| M/F | P.O. | > 150 to < 500 |
Subacute and Chronic Toxicity
| SPECIES | ROUTE | DOSE mg/kg/day | #ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 125 250 500 | 5 F 5 M | 2 weeks | No abnormalities. |
| Rat | Oral | 0 25 75 225 | 15 F 15 M | 13 weeks | Increased salivation in some rats in the 75 and 225 mg/kg groups. Increased blood glucose levels in high dosage groups. Increased alkaline phosphatase levels in the 225-mg/kg group. Significantly greater relative liver weights. |
| Rat | Oral | 0 20 60 300 | 15 F 15 M | 26 weeks | Food intake slightly reduced in females receiving 20 and 300 mg/kg; body weight gain also depressed in females on 300 mg/kg. |
| SPECIES | ROUTE | DOSE mg/kg/day | #ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 20 60 300 | 40 F 40 M | 78 weeks | Reduced grooming activity, decreased body weight gain and food intake in the 300-mg/kg group. |
| Rat | I.V. | 0 2 20 | 10 F 10 M | 4 weeks (5 days/ week) | Reduction of packed cell volume and haemoglobin levels in males at 20 mg/kg. Blood glucose decreased in treated males and sodium increased in the 20 mg/kg male group. Blood urea and potassium increased in females at 20 mg/kg. |
| Rat | I.V. | 0 5 15 40 | 10 F 10 M | 4 weeks | Rats at 40 mg/kg collapsed within S seconds of dosing; all recovered within 2 minutes. Increased urine output and spleen weight at 40 mg/kg. Mild inflammatory reaction at injection sites |
| Dog | Oral | 0 15 41 113 | 3 F 3 M | 13 weeks | Dose-related salivation and emesis. Two deaths at 113 mg/kg. SGOT SGPT increased and protein levels reduced in the 41 and 113 mg/kg groups. Mammary hyperplasia in two females at 113 |
| mg/kg. | |||||
| Dog | Oral | 0 20 40 110 | 3 F 3 M | 26 weeks | Excessive salivation and occasional emesis at 110 mg/kg. ECG recording showed prolonged slowing of heart rate; some dogs at 40 mg/kg also had delayed A-V conduction |
| Dog | Oral | 0 20 40 110 | 4 F 4 M | 52 weeks | Occasional vomiting at all dose levels. Sedation and salivation mainly in dogs receiving 110 mg/kg. Prolonged, dose-related reduction in heart rate and increase in PR interval. Increase in serum potassium at 110 mg/kg One dog also had elevated SGPT and SGOT levels on 110 mg/kg. |
| Dog | I.V. | 0 2 20 | 2 F 2 M | 4 weeks | Vomiting at 20 mg/kg. Treated groups gained significantly less weight than controls. Sporadic variations in blood urea and serum potassium. |
| Dog | I.V. | 0 5 30 | 4 F 4M | 4 weeks | Dose-related unsteadiness retching and vomiting immediately after dosing. One female dog died on the high dose. |
Carcinogenicity studies
Groups of 50 male and 50 female albino rats of the CD F/Crl BR strain received, in the diet, respectively 0, 100 and 300 mg/kg/day of acebutolol hydrochloride for 78 weeks. All groups were then off medication until the study terminated at 106 weeks. Groups of 60 male and 60 female CFLP mice, received 0, 20, 60 and 300 mg/kg/day of the drug for 87 weeks in a similar study.
There were no overt signs of toxicity. The incidence of tumors in acebutolol hydrochloride treated animals was no greater than that for the controls.
Diacetolol, the major metabolite of acebutolol HCl in man, was tested for carcinogenicity in rats of the CD strain. Groups of 85 males and 85 females received, in the diet during 104 weeks, doses of 100, 500 or 3,000 mg/kg/day; 145 animals of each sex were used as controls. No carcinogenic potential was observed.
Acebutolol Hydrochloride and diacetolol were also shown to be devoid of mutagenic potential in the Ames test.
Teratogenicity Studies
- a) Acebutolol
| SPECIES | ROUTE | DOSE mg/kg/day | # ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 12 60 | 16 17 17 | Day 6-16 of gestation | No teratogenicity or embryotoxicity seen. |
| Rat | I.V. | 0 2 6 18 | 15 16 15 15 | Day 5-17 of gestation | No teratogenicity or embryotoxicity seen. |
| Rabbit | Oral | 0 12 60 | 15 16 17 | Day 6-16 of gestation | No teratogenicity or embryotoxicity seen. |
| Rabbit | I.V. | 0 2 6 18 | 15 14 15 14 | Day 5-20 of gestation | Foetal abnormalities, not previously encountered in the strain of rabbits used, were observed at 6 and 18 mg/kg: rib defects, gastroschisis, ventricular septal defect, dysplasia of urogenital system and umbilical hernia |
| Rabbit | I.V. | 0 6 | 11 15 | Day 5-20 of gestation | Mean live foetal weight significantly reduced at 6 mg/kg. No teratogenicity |
| 18 | 17 | or embryotoxicity seen. |
- b) Diacetolol
| SPECIES | ROUTE | DOSE mg/kg/day | # ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 50 300 1, 800 | 25 | Day 5-17 of gestation | Non-statistically significant increase in incidence of bilateral cataracts in foetuses from dams treated with 1,800 mg/kg/day. |
| Rabbit | Oral | 0 50 150 450 | 18 18 18 19 | Day 5-20 of gestation | Increase in post-implantation loss (reduced food consumption and weight gain) at 450 mg/kg/day. No teratogenicity seen. |
Peri- and Post-natal Study
| SPECIES | ROUTE | DOSE mg/kg/day | # ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 50 100 200 | 20 | From day 15 of gestation to day 12 of lactation | Post-natal deaths were significantly higher in the three acebutolol groups (ceased lactation in a few rats). The length of gestation was also slightly increased. |
Reproduction Study
- a) Acebutolol
| SPECIES | ROUTE | DOSE mg/kg/d ay | # ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 40 240 | 13 M 25 F | Males * Females ** | Reduction in food intake in the 240 mg/kg treated group and a dose-related reduction in weight gain in the first generation rats on day 14 of gestation. No evidence of teratogenicity or adverse effect on maternal behaviour, lactation or general reproductive performance. |
- b) Diacetolol
| SPECIES | ROUTE | DOSE mg/kg/day | # ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
| Rat | Oral | 0 40 200 1000 | 15 M 30 F | Males * Females ** | No significant impact on reproductive performance or fertility. |
* males: for 9 weeks prior to mating
** females: for 2 weeks prior to mating through gestation and lactation (2 generations)
References
- 1.
ASHTON, W.L.
An open, multicentre study of acebutolol in hypertension.
Current Medical Research and Opinion, Vol. 4, No. 6, 1976.
- 2.
ASHTON, W.L.
Acebutolol (400 mg) given as a single daily dose to hypertensive patients previously stabilized on 400 mg acebutolol daily in divided doses: an open multicentre study. Current Medical Research and Opinion. Vol. 5, No. 4 1978, pp. 347-3 53.
- 3.
BASIL, B. et al.
β-adrenoceptor blocking properties and cardioselectivity of M&B 17,803A. British Journal of Pharmacology, Vol. 48, No. 2, June 1973, pp. 198-211.
- 4.
BASIL, B. et al.
A comparison of the experimental anti-arrhythmic properties of acebutolol (M&B 17, 803A) propranolol and practolol.
British Journal of Pharmacology, Vol. 50, 1974, pp. 323-333.
- 5.
BIRON, P. et al.
Acebutolol: basis for the prediction of effect on exercise tolerance. Clin. Pharmacol. Ther., Vol. 19, No. 3, 1976, pp. 333-338.
- 6.
COLEMAN, A.J. et al.
The selective action of β-adrenoceptor blocking drugs and the nature of β1 and β2 adrenoceptors.
British J. Pharmac., Vol. 59, 1977, pp. 83-93.
- 7.
CUTHBERT, M.F. et al.
The effect of M&B 17,803A, a new β-adrenoceptor antagonist, on the cardiovascular responses to tilting and isoprenaline in man.
J. de Pharmacologie, Paris, 31 mars, ler et 2 avril 1971, pp. 197-198.
- 8.
FILLASTRE, J.P. et al.
Acebutolol in the treatment of essential hypertension: results after two years administration. N. Presse Médicale, Vol. 4, No. 46, Suppl. 1975, pp. 3282-86.
- 9.
GOTSMAN, MS. et al.
The treatment of angina pectoris. An objective assessment of oral acebutolol (Sectral). Clin. Trials
J., Vol. 11, No. 3, Suppl. 1974, pp. 80-85.
- 10.
HANSSON, L.
Controlled trial of acebutolol in hypertension.
Eur. J. Clin. Pharmacol., Vol. 12, 1977, pp. 89-92.
- 11.
KHAMBATTA, R.B.
Patients with angina pectoris: comparison of a new β-receptor blocking agent acebutolol (Sectral) and propranolol.
Clin. Trials J., Vol. 11, 1974, pp. 59-67.
- 12.
LEARY, W.P.
Respiratory effects of acebutolol hydrochloride.
S.A. Medical J., Vol. 47, July 2 1st, 1973, pp. 1245-48.
- 13.
LEARY, W.P. et al.
Treatment of hypertension with single daily doses of acebutolol.
South African Medical Journal. Vol. 53, No. 15, April 15, 1978, pp. 579-581.
- 14.
LEDUC, G.C. et al.
The use of oral acebutolol in angina pectoris.
Clin. Trials, J., Vol. 11, No. 3, Suppl. 1974, pp. 711-79.
- 15.
LETAC, B. et al.
Treatment of essential hypertension by acebutolol: double-blind study against placebo. Nouv. Presse Méd, Vol. 4, No. 46, Suppl. 1975, pp. 3273-77.
- 16.
MacDONALD, IA. et al.
A comparison study of acebutolol, a cardiospecific 13-adrenergic blocker, and propranolol in the treatment of angina pectoris.
Current Therapeutic Research. Vol. 24, No. 5, September 1978.
- 17.
ROUX, A. et al.
Study of acebutolol dialysis and pharmacokinetics data concerning patients with renal insufficiency undergoing haemodialysis.
Nouvelle Presse Médicale, Vol. 4, No. 45, Suppl. 1975, pp. 3228-33.
- 18.
TREMBLAY, G. et al.
Dissociation between clinical and exercise responsiveness to 13-blockage in angina. Int. J. Clin. Pharmacology. Vol. 15, No. 11, 1978, p. 508-5 12.