


Product Monograph - Nucala (Glaxosmithkline, 100 mg, 40 mg)
Recent Major Label Changes
| 1 Indications | 2026-06 |
|---|---|
| 1 Indications, 1.1 Pediatrics | 2026-06 |
| 1 Indications, 1.2 Geriatrics | 2026-06 |
| 4 Dosage and Administration, 4.2 Recommended Dose & Dosage Adjustment | 2026-06 |
| 7 Warnings and Precautions, General | 2026-06 |
| 7 Warnings and Precautions, Immune | 2026-06 |
| 7 Warnings and Precautions, 7.1.3 Pediatrics | 2026-06 |
| 7 Warnings and Precautions, 7.1.4 Geriatrics | 2026-06 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 5
- 1.
Indications ....................................................................................................................... 5
1.1. Pediatrics .................................................................................................................. 5
1.2. Geriatrics .................................................................................................................. 6
- 2. Contraindications ............................................................................................................ 6
- 4.
Dosage and Administration ............................................................................................. 6
4.1. Dosing Considerations .............................................................................................. 6
4.2. Recommended Dose and Dosage Adjustment ......................................................... 7
4.3. Reconstitution .......................................................................................................... 8
4.4. Administration .......................................................................................................... 9
4.5. Missed Dose ........................................................................................................... 10
- 5. Overdose ....................................................................................................................... 10
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................. 10
- 7.
Warnings and Precautions ............................................................................................. 12
General ............................................................................................................................... 12
Immune .............................................................................................................................. 12
7.1. Special Populations ................................................................................................ 13
7.1.1. Pregnancy ...................................................................................................... 13
7.1.2. Breastfeeding ................................................................................................ 13
7.1.3. Pediatrics ....................................................................................................... 13
7.1.4. Geriatrics ....................................................................................................... 13
- 8.
Adverse Reactions ......................................................................................................... 14
8.1. Adverse Reaction Overview .................................................................................... 14
8.2. Clinical Trial Adverse Reactions .............................................................................. 14
8.3. Less Common Clinical Trial Adverse Reactions ....................................................... 30
8.5. Post-Market Adverse Reactions ............................................................................. 30
- 9.
Drug Interactions ........................................................................................................... 31
9.2. Drug Interactions Overview .................................................................................... 31
9.4. Drug-Drug Interactions ........................................................................................... 31
9.5. Drug-Food Interactions........................................................................................... 31
9.6. Drug-Herb Interactions ........................................................................................... 31
9.7. Drug-Laboratory Test Interactions ......................................................................... 31
- 10.
Clinical Pharmacology ................................................................................................... 31
10.1. Mechanism of Action .............................................................................................. 31
10.2. Pharmacodynamics ................................................................................................ 31
10.3. Pharmacokinetics ................................................................................................... 33
10.4. Immunogenicity ...................................................................................................... 35
- 11. Storage, Stability, and Disposal ...................................................................................... 36
- 12. Special Handling Instructions ......................................................................................... 36
Part 2: Scientific Information ................................................................................................ 37
- 13. Pharmaceutical Information .......................................................................................... 37
- 14.
Clinical Trials .................................................................................................................. 37
14.1. Clinical Trials by Indication ..................................................................................... 37
Severe Eosinophilic Asthma ................................................................................................ 37
Chronic Rhinosinusitis with Nasal Polyps ............................................................................ 43
Chronic Obstructive Pulmonary Disease ............................................................................. 48
Eosinophilic Granulomatosis with Polyangiitis .................................................................... 52
Hypereosinophilic Syndrome .............................................................................................. 57
- 16. Non-Clinical Toxicology .................................................................................................. 60
Patient Medication Information ........................................................................................... 61
Patient Medication Information ........................................................................................... 68
INSTRUCTIONS FOR USE - Pre-Filled Autoinjector ................................................................. 76
INSTRUCTIONS FOR USE – 100 mg/mL Pre-Filled Syringe (SAFETY SYRINGE) ......................... 83
INSTRUCTIONS FOR USE – 40 mg/0.4 mL Pre-Filled Syringe (SAFETY SYRINGE) ..................... 90
Part 1: Healthcare Professional Information
1. Indications
Severe Eosinophilic Asthma
NUCALA (mepolizumab for injection, mepolizumab injection) is indicated as add-on maintenance treatment for adults, adolescents, and children (aged 6 years and older) with severe eosinophilic asthma who:
- are inadequately controlled with high-dose inhaled corticosteroids (patients ≥ 18 years of age) or medium-to-high-dose inhaled corticosteroids (patients 6-17 years of age) and an additional asthma controller(s) (e.g., LABA); and
- have a blood eosinophil count of ≥ 150 cells/mcL (0.15 GI/L) at initiation of treatment with NUCALA OR ≥ 300 cells/mcL (0.3 GI/L) in the past 12 months.
NUCALA is not indicated for the relief of acute bronchospasm or status asthmaticus (See 7 Warnings and Precautions).
Chronic Rhinosinusitis with Nasal Polyps
NUCALA is indicated as add-on maintenance treatment with intranasal corticosteroids in adult patients with severe chronic rhinosinusitis with nasal polyps (CRSwNP) inadequately controlled by intranasal corticosteroids alone.
Chronic Obstructive Pulmonary Disease
NUCALA is indicated as add-on maintenance treatment in adult patients with chronic obstructive pulmonary disease (COPD) characterized by raised blood eosinophils inadequately controlled by the combination of an inhaled corticosteroid (ICS), a long-acting beta2-agonist (LABA), and a long-acting muscarinic antagonist (LAMA).
NUCALA is not indicated for the relief of acute bronchospasm (See 7 Warnings and Precautions).
Eosinophilic Granulomatosis with Polyangiitis
NUCALA is indicated as an add-on to corticosteroids for the treatment of adult patients with eosinophilic granulomatosis with polyangiitis (EGPA).
Hypereosinophilic Syndrome
NUCALA is indicated as an add-on to standard therapy for the treatment of adult patients with hypereosinophilic syndrome (HES) for ≥6 months without an identifiable non-hematologic secondary cause.
1.1. Pediatrics
Severe Eosinophilic Asthma: NUCALA is not indicated in patients under 6 years of age. There is limited efficacy and safety experience with NUCALA in patients less than 18 years of age (see 14 Clinical Trials).
Dosing in children was derived using modelling and simulation of adult and pediatric PK data (see 10.3 Pharmacokinetics).
Chronic Rhinosinusitis with Nasal Polyps: NUCALA is not indicated in patients under 18 years of age.
Chronic Obstructive Pulmonary Disease: NUCALA is not indicated in patients under 18 years of age.
Eosinophilic Granulomatosis with Polyangiitis: NUCALA is not indicated in patients under 18 years of age.
Hypereosinophilic Syndrome: NUCALA is not indicated in patients under 18 years of age.
1.2. Geriatrics
Of the 3648 patients that received NUCALA 100 mg SC, 929 (25%) were 65 years of age and older and 205 (6%) were 75 years of age and older. Efficacy and safety in this age group was consistent with the overall study population (see 10.3 Pharmacokinetics).
2. Contraindications
NUCALA is contraindicated in patients who are hypersensitive to mepolizumab, to any ingredient(s) in the formulations, or component(s) of the containers. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
NUCALA should only be administered as a subcutaneous injection.
NUCALA is intended for use under the guidance of a physician who is experienced in the monitoring of signs and symptoms of hypersensitivity after administration of biologic agents.
Lyophilized powder
NUCALA (mepolizumab for injection) should be reconstituted and administered by a qualified healthcare professional who is prepared to manage anaphylaxis that can be life-threatening (see 7 Warnings and Precautions). Following reconstitution, NUCALA should be used immediately upon withdrawal from the vial into a syringe (see 4.4 Administration).
This dosage form is acceptable to deliver a 40 mg and 100 mg dose.
Solution in 100 mg/mL pre-filled autoinjector or pre-filled syringe (safety syringe)
NUCALA (mepolizumab injection) may be self-administered by the patient or administered by a caregiver if their healthcare professional determines that it is appropriate and the patient or caregiver are trained in injection techniques (see 4.4 Administration).
The 100 mg/mL pre-filled autoinjector and pre-filled syringe deliver a 100 mg dose of mepolizumab, and are not suitable for those who require a 40 mg dose of mepolizumab (i.e. children 6 to 11 years of age with severe eosinophilic asthma).
Solution in 40 mg/0.4 mL pre-filled syringe (safety syringe)
NUCALA (mepolizumab injection) must be administered by a healthcare professional or a caregiver. It may be administered by a caregiver if a healthcare professional determines that it is appropriate and the caregiver is trained in injection techniques (see 4.4 Administration).
The 40 mg/0.4 mL pre-filled syringe delivers a 40 mg dose of mepolizumab and is only for use in children aged 6 to 11 years of age with severe eosinophilic asthma.
4.2. Recommended Dose and Dosage Adjustment
Severe Eosinophilic Asthma:
Adults and Adolescents (≥ 12 years of age):
The recommended dose of NUCALA is 100 mg administered subcutaneously once every 4 weeks.
Children (6-11 years of age): The recommended dose of NUCALA is 40 mg administered subcutaneously once every 4 weeks.
Only the lyophilized powder formulation or the 40 mg/0.4 mL pre-filled syringe can provide the recommended 40 mg dose for children 6 to 11 years of age (see 4.4 Administration).
Each vial of lyophilized powder should be used for a single patient, and any remainder in the vial should be discarded.
Chronic Rhinosinusitis with Nasal Polyps:
The recommended dose of NUCALA is 100 mg administered subcutaneously once every 4 weeks.
Chronic Obstructive Pulmonary Disease:
The recommended dose of NUCALA is 100 mg administered subcutaneously once every 4 weeks.
Eosinophilic Granulomatosis with Polyangiitis:
The recommended dose of NUCALA is 300 mg administered subcutaneously once every 4 weeks.
The 300 mg dose for treatment of Eosinophilic Granulomatosis with Polyangiitis requires the administration of 3 separate 100 mg injections (see 4.4 Administration).
Hypereosinophilic Syndrome:
The recommended dose of NUCALA is 300 mg administered subcutaneously once every 4 weeks.
The 300 mg dose for treatment of hypereosinophilic syndrome requires the administration of 3 separate 100 mg injections (see 4.4 Administration).
Geriatrics
No dosage adjustment is required for elderly patients (see 10.3 Pharmacokinetics).
Pediatrics
Severe Eosinophilic Asthma: NUCALA is not indicated in patients under 6 years of age.
Dosing in children was derived using modelling and simulation of adult and pediatric PK data (see 10.3 Pharmacokinetics).
Chronic Rhinosinusitis with Nasal Polyps: NUCALA is not indicated in patients under 18 years of age.
Chronic Obstructive Pulmonary Disease: NUCALA is not indicated in patients under 18 years of age.
Eosinophilic Granulomatosis with Polyangiitis: NUCALA is not indicated in patients under 18 years of age.
Hypereosinophilic Syndrome: NUCALA is not indicated in patients under 18 years of age.
Hepatic Insufficiency
Dosage adjustments in patients with hepatic impairment are unlikely to be required (see 10.3 Pharmacokinetics).
Renal Insufficiency
Dosage adjustments in patients with renal impairment are unlikely to be required (see 10.3 Pharmacokinetics).
4.3. Reconstitution
Lyophilized powder
Instructions for reconstitution: NUCALA does not contain a preservative, therefore, reconstitution should be carried out by a healthcare professional under aseptic conditions.
- 1. Reconstitute the NUCALA powder in the vial with 1.2 mL of sterile Water for Injection, preferably using a 2 to 3 mL syringe and a 21 gauge to 27 gauge needle. The reconstituted solution will contain a concentration of 100 mg/mL mepolizumab and may appear colourless to pale yellow or pale brown. Do not mix with other medications.
- 2.
The stream of sterile Water for Injection should be directed vertically onto the centre of the lyophilized cake. Allow the vial to sit at room temperature during reconstitution, gently swirling the vial for 10 seconds with circular motion at 15-second intervals until the powder is dissolved. Reconstitution is typically complete within 5 minutes after the sterile water has been added, but it may take additional time.
Note: Do not shake the reconstituted solution during the procedure as this may lead to excessive foaming or precipitation.
- 3. If a mechanical reconstitution device (swirler) is used to reconstitute NUCALA, reconstitution can be accomplished by swirling at 450 rpm for no longer than 10 minutes. Alternatively, swirling at 1000 rpm for no longer than 5 minutes is acceptable.
- 4. Visually inspect the reconstituted NUCALA for particulate matter and clarity prior to use. The solution should be clear to opalescent, and colourless to pale yellow or pale brown, free of visible particles. Small air bubbles or mild foaming are expected, however, and are acceptable. If particulate matter remains in the solution, or if the solution appears cloudy or milky, the solution must not be used.
- 5. If more than one vial is required for administration of the prescribed dosage, repeat steps 1 to 4.
- 6.
If the reconstituted solution of NUCALA in the vial is not used immediately:
- Store below 30°C.
- Do not freeze.
- Discard if not used within 8 hours of reconstitution.
4.4. Administration
Lyophilized powder
Instructions for administration of each 100 mg dose: For subcutaneous administration, a 1 mL polypropylene syringe fitted with a disposable needle 21 gauge to 27 gauge x 0.5 inch (13 mm) should preferably be used.
- 1. Just prior to administration, remove 1 mL of reconstituted NUCALA. Do not shake the reconstituted NUCALA solution during the procedure as this could lead to product foaming or precipitation.
- 2. Administer the 1 mL injection (equivalent to 100 mg mepolizumab) subcutaneously into the upper arm, thigh, or abdomen.
If more than one vial is required for administration of the prescribed dosage, repeat steps 1 to 2. Injection sites should be at least 5 cm apart.
Instructions for administration of each 40 mg dose: For subcutaneous administration, a 1 mL polypropylene syringe fitted with a disposable needle 21 gauge to 27 gauge x 0.5 inch (13 mm) should preferably be used.
- 1. Just prior to administration, remove 0.4 mL of reconstituted NUCALA. Do not shake the reconstituted NUCALA solution during the procedure as this could lead to product foaming or precipitation. Dispose of the remaining solution.
- 2. Administer the 0.4 mL injection (equivalent to 40 mg mepolizumab) subcutaneously into the upper arm, or thigh.
Solution in pre-filled autoinjector or pre-filled syringe (safety syringe)
A patient may self-inject or the caregiver may administer NUCALA injection subcutaneously after the healthcare professional determines it is appropriate. The healthcare professional should provide the patient or caregiver with proper training in injection technique and on the instructions for administration prior to use.
The 100 mg/mL pre-filled autoinjector and pre-filled syringe deliver a 100 mg dose of mepolizumab, and are not suitable for those who require a 40 mg dose of mepolizumab.
The 40 mg/0.4 mL pre-filled syringe delivers a 40 mg dose of mepolizumab and is suitable for those who require this dose, i.e. children 6 to 11 years of age with severe eosinophilic asthma.
Ensure the respective PATIENT MEDICATION INFORMATION and INSTRUCTIONS FOR USE are followed.
Instructions for administration:
- 1. Remove the pre-filled autoinjector or pre-filled syringe from the refrigerator and allow it to sit at room temperature for 30 minutes prior to injection. Do not warm NUCALA in any other way.
- 2.
Prior to administration, visually inspect the window of the pre-filled autoinjector or the pre-filled syringe for particulate matter or discoloration. NUCALA injection should be clear to opalescent, colourless to pale yellow or pale brown in color. Do not use NUCALA injection if the product
- exhibits discoloration, cloudiness, or particulate matter. Do not use the NUCALA pre-filled autoinjector or pre-filled syringe if dropped on a hard surface.
- 3. Administer the subcutaneous injection into the thigh or abdomen, avoiding the 5 cm (2 inches) around the navel. The upper arm can also be used if a caregiver administers the subcutaneous injection.
- 4. For use in EGPA and HES, make sure the injection sites for each subcutaneous injection are separated by at least 5 cm (2 inches).
- 5. Never give injections into areas where the skin is tender, bruised, red, or hard.
4.5. Missed Dose
Lyophilized powder
If a dose is missed or the patient is unable to attend an appointment for one of the injections, the missed dose should be administered as soon as possible.
Solution in pre-filled autoinjector or pre-filled syringe (safety syringe)
If a dose is missed, instruct the patient or patient caregiver to administer a dose as soon as possible. Thereafter, the patient can resume dosing on the usual day of administration. If the next dose is already due, then administer as planned.
5. Overdose
There is no clinical experience with overdose of NUCALA.
Single doses of up to 1500 mg were administered intravenously in a clinical trial to patients with eosinophilic disease without evidence of dose-related toxicities.
Treatment
There is no specific treatment for an overdose with NUCALA. If overdose occurs, the patient should be treated supportively with appropriate monitoring as necessary.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 Dosage Forms, Strengths, Composition and Packaging
NUCALA is available in the following formats:
Lyophilized powder
NUCALA is available as a sterile preservative-free, lyophilized powder for subcutaneous injection. NUCALA is presented in a single-use 10 mL type I glass vial with a bromobutyl rubber (latex-free) stopper and a grey aluminum overseal with a plastic flip-cap.
Each single-use vial contains 144 mg of lyophilized mepolizumab. Upon reconstitution with 1.2 mL of sterile Water for Injection, USP, each vial delivers 100 mg mepolizumab in 1 mL at a pH of 7.0.
This dosage form is acceptable to deliver a 40 mg dose or a 100 mg dose.
Solution in pre-filled autoinjector or pre-filled syringes (safety syringe)
NUCALA is available as a sterile, clear to opalescent, colourless to pale yellow or pale brown, preservative-free solution for subcutaneous use. It is supplied in the following formats:
- A single-dose, 1-mL, pre-filled autoinjector with a fixed 29 gauge, half-inch needle;
- A single-dose, 1-mL, pre-filled syringe with a fixed 29 gauge, half inch needle with a needle guard.
- A single dose, 0.4 mL, pre-filled syringe with a fixed 29 gauge, half inch needle with a needle guard.
Each 1 mL pre-filled autoinjector or pre-filled syringe delivers 100 mg mepolizumab at a pH of 6.3. Neither are suitable for those who require a 40 mg dose of mepolizumab.
Each 0.4 mL pre-filled syringe delivers 40 mg mepolizumab at a pH of 6.3, which is suitable for those who require a 40 mg dose of mepolizumab.
Description
NUCALA (mepolizumab for injection and mepolizumab injection) is a humanised IgG1 kappa monoclonal antibody that binds with high affinity and specificity to soluble interleukin-5 (IL-5).
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| subcutaneous injection | Lyophilized powder for subcutaneous injection. Each single-use vial contains 100 mg/mL mepolizumab after reconstitution. | Polysorbate 80, sodium phosphate dibasic heptahydrate, and sucrose. |
Solution for subcutaneous injection. Each single-use pre-filled autoinjector contains 100 mg/mL mepolizumab. Single-use pre-filled syringes contain either 40 mg/ 0.4 mL or 100 mg/mL mepolizumab. | Citric acid monohydrate, EDTA disodium dihydrate, polysorbate 80, sodium phosphate dibasic heptahydrate, and sucrose. |
Mepolizumab has a molecular weight of approximately 149 kDa and is produced by recombinant DNA technology in Chinese hamster ovary cells.
7. Warnings and Precautions
General
Acute Asthma or Chronic Obstructive Pulmonary Disease Symptoms or Deteriorating Disease
NUCALA should not be used to treat acute asthma or COPD exacerbations.
Asthma-related or COPD-related adverse events or exacerbations may occur during treatment with NUCALA. Patients should be instructed to seek medical advice if their asthma or COPD remains uncontrolled or worsens after initiation of treatment with NUCALA.
Corticosteroid Reduction
Abrupt discontinuation of corticosteroids after initiation of NUCALA therapy is not recommended. Reductions in corticosteroid doses, if required, should be gradual and performed under the supervision of a physician.
Hypereosinophilic Syndrome Subgroup Diagnosis
Due to the differential treatment regimens between HES subgroups, genetic testing for the FIP1L1-PDGFRα mutation should be completed to aid in the determination of HES variant and to guide optimal treatment decision.
COPD patients with low blood eosinophil counts
There is insufficient data to support the efficacy and safety of NUCALA in COPD patients with a blood eosinophil count <150 cells/mcL and no evidence of a blood eosinophil count ≥300 cells/mcL in the previous 12 months.
Immune
Hypersensitivity and Administration-Related Reactions
Acute and delayed systemic reactions, including hypersensitivity reactions (e.g., anaphylaxis, urticaria, angioedema, rash, bronchospasm, hypotension), have occurred following administration of NUCALA. These reactions generally occur within hours of administration, but in some instances had a delayed onset (i.e., days). These reactions may occur for the first time after a long duration of treatment.
Parasitic Infections
Eosinophils may be involved in the immunological response to some helminth infections. Patients with pre-existing helminth infections were excluded from participation in the clinical program. Patients with pre-existing helminth infections should be treated for their infection prior to initiating therapy with NUCALA. If patients become infected whilst receiving treatment with NUCALA and do not respond to recommended anti-helminth treatment, temporary discontinuation of NUCALA should be considered.
Opportunistic Infection by Herpes Zoster
In controlled clinical trials, three serious adverse reactions of herpes zoster occurred in subjects receiving NUCALA compared with 1 subject receiving placebo (see 8 Adverse Reactions). Consider vaccination if medically appropriate prior to starting therapy with NUCALA.
7.1. Special Populations
7.1.1. Pregnancy
No studies have been conducted with NUCALA in pregnant women, and there are no fertility data in humans (see 16 Non-Clinical Toxicology). In clinical trials there were too few pregnancies reported to inform on maternal and fetal health and development outcomes.
NUCALA should not be used by pregnant women, unless the expected benefit to the mother justifies the potential risk to the fetus. Women should be advised to contact their physicians if they become pregnant while receiving NUCALA, or during the 4 months after treatment is stopped.
7.1.2. Breastfeeding
There are no data regarding the presence of mepolizumab in human milk, the effects on the breastfed infant, or the effects on milk production (see 16 Non-Clinical Toxicology).
A decision should be made whether to discontinue breast-feeding or discontinue NUCALA, taking into account the importance of breast-feeding to the infant and the importance of the drug to the mother.
7.1.3. Pediatrics
Pediatrics (< 18 years of age):
Patients less than 6 years of age were not included in the severe eosinophilic asthma clinical trials with NUCALA. There is limited efficacy and safety experience with NUCALA in pediatric patients less than 18 years of age. A total of 28/1327 (2.1%) patients age 12 to 17 years old were enrolled in the placebo-controlled severe asthma clinical trials with NUCALA; and 36 patients age 6 to 11 years old were enrolled in the uncontrolled severe asthma clinical trial with NUCALA.
Patients less than 18 years of age were not included in the chronic rhinosinusitis with nasal polyps clinical trial with NUCALA.
Patients less than 18 years of age were not included in the chronic obstructive pulmonary disease clinical trials with NUCALA.
Patients less than 18 years of age were not included in the eosinophilic granulomatosis with polyangiitis clinical trial with NUCALA.
NUCALA is not indicated for hypereosinophilic syndrome in patients under 18 years of age.
7.1.4. Geriatrics
Severe eosinophilic asthma: A total of 119/1,327 (9.0%) patients age 65 and older were enrolled in the placebo-controlled severe asthma clinical trials with NUCALA.
CRSwNP: A total of 56/407 (14%) patients age 65 and older were enrolled in the chronic rhinosinusitis with nasal polyps clinical trial with NUCALA.
COPD: A total of 614/1043 (59%) patients age 65 and older were enrolled in the COPD clinical trials with NUCALA.
EGPA: A total of 17/136 (13%) patients age 65 and older were enrolled in the eosinophilic granulomatosis with polyangiitis clinical trial with NUCALA.
HES: A total of 14/108 (13%) patients age 65 and older were enrolled in the hypereosinophilic syndrome clinical trial with NUCALA.
No dosage adjustment is required in patients 65 years or older (see 10.3 Pharmacokinetics).
8. Adverse Reactions
8.1. Adverse Reaction Overview
In clinical studies that enrolled adult and adolescent patients with severe eosinophilic asthma, the most commonly reported adverse drug reactions (events considered to be possibly related to treatment with mepolizumab) during treatment with NUCALA were headache, injection site reaction, and back pain. In a clinical study that enrolled children with severe eosinophilic asthma, the most commonly reported adverse drug reactions were headache, injection site reaction, abdominal pain upper, eczema, and pharyngitis.
In clinical studies that enrolled adult patients with chronic rhinosinusitis with nasal polyps, chronic obstructive pulmonary disease, eosinophilic granulomatosis with polyangiitis and hypereosinophilic syndrome, the most commonly reported adverse drug reaction during treatment with NUCALA was headache.
Hypersensitivity reactions, including anaphylaxis, swelling of the face, mouth, and/or tongue; fainting, dizziness, or lightheadedness; hives; breathing problems; and rash have been reported within hours or days of receiving treatment with NUCALA.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Severe Eosinophilic Asthma
Adults and Adolescents (≥ 12 years of age)
The safety of mepolizumab has been studied in three randomized, placebo-controlled, multicentre clinical trials of 24 to 52 weeks duration and three open-label, uncontrolled, extension studies with a median treatment duration of 2.8 years (range 4 weeks to 4.5 years). A total of 1,327 adult and adolescent patients with severe eosinophilic asthma received either a subcutaneous (SC) dose or an intravenous (IV) dose of mepolizumab or placebo during randomized controlled trials. The safety profile was comparable between groups that received mepolizumab SC (NUCALA 100 mg) or IV (75 mg, 250 mg and 750 mg).
Two of the three placebo-controlled studies (MEA115588 and MEA115575) included NUCALA 100 mg SC. Adverse events from the placebo-controlled studies that were reported by 1% or more of patients with NUCALA 100 mg SC and that were reported more frequently than placebo (≥1% difference from placebo) are presented in Table 2.
Table 2 On-treatment Adverse Events with ≥1% incidence with NUCALA and ≥1% more common with NUCALA than placebo in adult and adolescent subjects with severe eosinophilic asthma from placebo-controlled studies (MEA115588 and MEA115575)
| Adverse Events1 | NUCALA 100 mg SC (N = 263) n (%) | Placebo (N = 257) n (%) |
|---|---|---|
| Eye disorders | ||
| Lacrimation increased | 4 (1.5%) | 0 |
| Gastrointestinal disorders | ||
| Gastroesophageal reflux disease | 8 (3.0%) | 3 (1.2%) |
| Dry mouth | 4 (1.5%) | 0 |
| Gastrointestinal disorder | 3 (1.1%) | 0 |
| General disorders and administration site conditions | ||
| Injection site reaction2 | 21 (8.0%) | 8 (3.1%) |
| Chest pain | 5 (1.9%) | 2 (0.8%) |
| Local swelling | 3 (1.1%) | 0 |
| Infections and infestations | ||
| Urinary tract infection | 10 (3.8%) | 5 (1.9%) |
| Pharyngitis | 7 (2.7%) | 4 (1.6%) |
| Injury, poisoning and procedural complications | ||
| Ligament sprain | 3 (1.1%) | 0 |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 16 (6.1%) | 13 (5.1%) |
| Back pain | 16 (6.1%) | 9 (3.5%) |
| Muscle spasms | 7 (2.7%) | 1 (0.4%) |
| Musculoskeletal pain | 4 (1.5%) | 1 (0.4%) |
| Neck pain | 4 (1.5%) | 0 |
| Musculoskeletal stiffness | 3 (1.1%) | 0 |
| Tendonitis | 3 (1.1%) | 0 |
| Nervous system disorders | ||
| Headache | 53 (20.2%) | 47 (18.3%) |
| Psychiatric disorders | ||
| Insomnia | 7 (2.7%) | 3 (1.2%) |
| Reproductive system and breast disorders | ||
| Dysmenorrhoea | 3 (1.1%) | 0 |
| Respiratory, thoracic and mediastinal disorders | ||
| Nasal congestion | 7 (2.7%) | 2 (0.8%) |
| Rhinorrhoea | 5 (1.9%) | 1 (0.4%) |
| Skin and subcutaneous tissue disorders | ||
| Eczema | 11 (4.2%) | 2 (0.8%) |
1 MedDRA Version 16.1
2 The most common symptoms associated with subcutaneous injections included: pain, erythema, swelling, itching, and burning sensation.
Adverse drug reactions in adult and adolescent patients (events considered to be possibly related to treatment with mepolizumab) were identified following evaluation of all data from the three randomized placebo-controlled trials and include: headache (very common; ≥1/10) and pharyngitis, lower respiratory tract infection, urinary tract infection, nasal congestion, upper abdominal pain, eczema, back pain, pyrexia, and injection site reactions (all common; ≥1/100 to <1/10).
The safety profile of NUCALA in a select subset of adult and adolescent subjects with severe eosinophilic asthma (n=998) who were tolerant to NUCALA and entered the open-label, uncontrolled, extension studies, and were treated with NUCALA 100 mg SC every 4 weeks for a median of 2.8 years (range 4 weeks to 4.5 years), was consistent to that observed in the placebo-controlled studies.
Pediatric Population (6 to 17 years of age)
The safety of mepolizumab in adolescents (12-17 years of age) with severe eosinophilic asthma has been studied in 37 patients enrolled in four placebo-controlled studies, including 27 enrolled in two of these studies (MEA115588 and MEA115575); safety data from these 27 adolescent patients are presented within the adult and adolescent dataset above.
The safety of mepolizumab in children (6 to 11 years of age) with severe eosinophilic asthma has been studied in 36 patients in an uncontrolled, open-label study (200363). Patients received NUCALA 40 mg SC (for a weight <40 kg) or 100 mg SC (for a weight ≥40 kg) once every 4 weeks, for 12 weeks (short-term phase). After a treatment interruption of 8 weeks, 30 children resumed NUCALA treatment for a further 52 weeks (long-term phase). No additional adverse reactions were reported in children treated with NUCALA compared to those reported in adult and adolescent patients enrolled in the severe asthma trials. Adverse events from this study that were reported in more than 1 patient receiving NUCALA are presented in Table 3.
Table 3 On-treatment Adverse Events, occurring in >1 child (6-11 years of age) with Severe Eosinophilic Asthma (Study 200363)
Short-Term Phase (12 weeks) | Long-Term Phase (52 weeks) | |||
|---|---|---|---|---|
Short-Term Phase (12 weeks) | Long-Term Phase (52 weeks) | |||
| Adverse Events1 | NUCALA SC (N=36) n (%) | Adverse Events2 | NUCALA SC (N=30) n (%) | |
| Gastrointestinal disorders | ||||
| Nausea | 3 (8) | Abdominal pain upper | 3 (10) | |
| Constipation | 2 (6) | Constipation | 2 (7) | |
| Vomiting | 2 (6) | Diarrhoea | 2 (7) | |
| General disorders and administration site conditions | ||||
| Injection site reaction | 5 (14) | Pyrexia | 2 (7) | |
| Pain | 2 (6) | - | - | |
| Infections and infestations | ||||
| Nasopharyngitis | 4 (11) | Bronchitis | 9 (30) | |
| Upper respiratory tract infection | 3 (8) | Nasopharyngitis | 6 (20) | |
| Lower respiratory tract infection | 2 (6) | Upper respiratory tract infection | 5 (17) | |
| Sinusitis | 2 (6) | Influenza | 4 (13) | |
| Viral upper respiratory tract infection | 2 (6) | Pharyngitis | 3 (10) | |
| - | - | Viral upper respiratory tract infection | 3 (10) | |
| - | - | Conjunctivitis | 2 (7) | |
| - | - | Ear infection | 2 (7) | |
| - | - | Gastroenteritis | 2 (7) | |
| - | - | Impetigo | 2 (7) | |
| - | - | Lower respiratory tract infection | 2 (7) | |
| - | - | Rhinitis | 2 (7) | |
| Musculoskeletal and connective tissue disorders | ||||
| - | - | Back pain | 2 (7) | |
| Nervous system disorders | ||||
| Headache | 5 (14) | Headache | 8 (27) | |
| Dizziness | 2 (6) | - | - | |
| Psychiatric disorders | ||||
| - | - | Aggression | 2 (7) | |
| Respiratory, thoracic and mediastinal disorders | ||||
| Asthma | 4 (11) | Asthma | 7 (23) | |
| Wheezing | 3 (8) | Cough | 3 (10) | |
| Oropharyngeal pain | 2 (6) | Epistaxis | 3 (10) | |
| Pharyngeal erythema | 2 (6) | - | - | |
| Skin and subcutaneous tissue disorders | ||||
| Rash | 2 (6) | Eczema | 3 (10) | |
| - | - | Dermatitis atopic | 2 (7) | |
| - | - | Rash | 2 (7) | |
1 MedDRA Version 19.1
2 MedDRA Version 20.1
Supplemental Adverse Event Information
The adult and adolescent data summarized below are from three completed placebo-controlled randomized clinical trials of 24 to 52 weeks duration that enrolled subjects with severe eosinophilic asthma who received either mepolizumab (NUCALA 100 mg SC or mepolizumab 75, 250 or 750 mg IV) or placebo. Data are presented for both the NUCALA (100 mg SC) treatment group and for all subjects receiving any dose of mepolizumab (referred to as the ‘mepolizumab all doses combined’ treatment group). Additionally, data from children (6 to 11 years of age) are presented for study 200363.
Fatalities
In placebo-controlled studies that enrolled adults and adolescents, 5 subjects died: 3 subjects (<1%) receiving mepolizumab (severe acute pancreatitis and septic shock in 1 subject receiving 250 mg IV; asthma in 1 subject receiving 250 mg IV; asphyxia due to suicide in 1 subject receiving 750 mg IV) and 2 subjects (<1%) receiving placebo (road traffic accident; aspiration and gastrointestinal hemorrhage). None of the deaths were considered related to study medication by the investigator.
There were no deaths reported in children receiving NUCALA from study 200363.
Serious Adverse Events
In placebo-controlled studies that enrolled adults and adolescents, serious adverse events were reported in 6% of subjects receiving NUCALA, 10% of subjects in the ‘mepolizumab all doses combined’ group, and 15% of subjects receiving placebo. Serious adverse events of asthma occurred in 2% of subjects receiving NUCALA, 5% of subjects in the ‘mepolizumab all doses combined’ group, and 9% of subjects receiving placebo.
Serious adverse events were reported in 17% and 23% of children receiving NUCALA in the short- and long-term phases of study 200363, respectively. Serious adverse events of asthma occurred in 8% and 17% of subjects, respectively.
Adverse Events leading to withdrawal from clinical trial
In placebo-controlled studies that enrolled adults and adolescents, 2% of subjects receiving NUCALA and 3% of subjects in the ‘mepolizumab all doses combined’ group withdrew due to an adverse event compared with 3% of subjects receiving placebo. The most frequent AE leading to withdrawal was asthma, which was reported by <1% of subjects in both the ‘mepolizumab all doses combined’ and placebo groups; no subjects receiving NUCALA withdrew due to asthma. Adverse events leading to withdrawal in subjects receiving NUCALA included atrial flutter (1 subject), injection site reaction (1 subject) and urticaria (1 subject). An additional subject was withdrawn after receiving one dose of NUCALA due to a pre-existing medical condition of left bundle branch block. Adverse events leading to withdrawal in the ‘mepolizumab all doses combined’ group occurring in more than one subject included hypersensitivity (3 subjects: 1 received 250 mg IV and 2 received 750 mg IV) and arthralgia (2 subjects: 1 received 75 mg IV and 1 received 250 mg IV).
One child receiving NUCALA withdrew from study 200363 due to worsening asthma.
Adverse Events of Special Interest
Systemic Allergic Reactions: In adults and adolescents, systemic hypersensitivity reactions were reported by 1% of subjects receiving NUCALA, 1% of subjects in the ‘mepolizumab all doses combined’ group and 2% of subjects receiving placebo. All hypersensitivity reactions were reported as mild or moderate severity.
Systemic hypersensitivity events were reported in 3% and 7% of children in the short- and long-term phases of study 200363, respectively. In the short-term phase, one child reported pruritus that was mild in intensity. In the long-term phase, one child reported rash and pruritus that were moderate in intensity, and one child reported a serious event of anaphylactic shock (anaphylactic shock due to peanut allergy) that was severe in intensity; anaphylactic shock was considered unrelated to NUCALA. All events resolved without NUCALA interruption.
Infections: In adults and adolescents, overall infections were reported with similar frequency in the NUCALA (52%), ‘mepolizumab all doses combined’ (57%), and placebo (58%) treatment groups. Serious infections were reported by 3% of subjects in the NUCALA, ‘mepolizumab all doses combined’, and placebo treatment groups. Serious infectious adverse events that were reported in more than one subject in the ‘mepolizumab all doses combined’ group included pneumonia (4 subjects: 1 received NUCALA, 1 received 75 mg IV, 2 received 750 mg IV compared to 3 who received placebo); lobar pneumonia (2 subjects received 75 mg compared to 1 who received placebo), and herpes zoster (2 subjects received NUCALA compared to 0 in the placebo group). Opportunistic infections were infrequent and were reported in <1% of subjects in the placebo group and in 1% of subjects receiving NUCALA. One subject receiving NUCALA reported a helminth infection of parasitic gastroenteritis, which resolved with treatment; NUCALA was continued.
Infection adverse events were reported in 50% and 73% of children treated with NUCALA in the short- and long-term phases of study 200363, respectively. Of these infections, 8% and 3% were serious, respectively.
Cardiovascular Events: In adults and adolescents, cardiac events were reported in 3% of placebo and ‘mepolizumab all doses combined’ patients, and 2% of patients that received mepolizumab 100 mg SC/75 mg IV. Serious cardiac events were reported in <1% of subjects in the NUCALA, ‘mepolizumab all doses combined’, and placebo treatment groups.
Vascular events were reported with similar frequency in the NUCALA (3%), ‘mepolizumab all doses combined’ (5%), and placebo (6%) treatment groups. Serious vascular events were reported in <1% in the ‘mepolizumab all doses combined’ group and 0% in both the NUCALA and placebo treatment groups.
No on-treatment cardiovascular events were reported in children enrolled in study 200363.
Injection Site Reactions: In adults and adolescents, injection site reactions were reported more frequently in the NUCALA group (8%) compared with the ‘mepolizumab all doses combined’, and placebo treatment groups (3% in both). Symptoms included mild or moderate rash, itching, swelling, burning, and pain at the injection site.
Injection site reactions were reported in 14% and 0% of children treated with NUCALA in the short- and long-term phases of study 200363, respectively. Symptoms were mild and included erythema, swelling, rash, itching, pain, and injection site wheal.
Neoplasms and Malignancies: In adults and adolescents, neoplasms were reported in 2% of subjects in the placebo group and <1% of subjects in both the NUCALA and the ‘mepolizumab all doses combined’ groups. Malignancies were reported in 3 subjects (<1%) in the placebo group and 2 subjects (<1%) in the ‘mepolizumab all doses combined’ group; no malignancies were reported in subjects receiving NUCALA. Malignancies reported during the studies included basal cell carcinoma, basosquamous carcinoma, prostate cancer, uterine cancer, and squamous cell carcinoma.
No neoplasms or malignancies were reported in children enrolled in study 200363.
Less Common Clinical Trial Adverse Reactions in Subjects with Severe Eosinophilic Asthma
In addition to the adverse events shown in Table 2, adverse events reported less commonly (defined as <1% in the ‘mepolizumab all doses combined’ treatment group) from the placebo-controlled severe asthma clinical trials in adults and adolescents and were reported in 2 or more patients receiving NUCALA compared to no reports in patients receiving placebo are summarized below.
Blood and lymphatic system disorders: iron deficiency anemia
Endocrine disorders: cushingoid
Eye disorders: lacrimation increased
Gastrointestinal disorder: dry mouth, gastrointestinal disorder
Injury, poisoning and procedural complications: administration related reaction, wrist fracture, stress fracture
Metabolism and nutrition disorders: diabetes mellitus, hypoglycemia, vitamin B12 deficiency
Musculoskeletal and connective tissue disorders: musculoskeletal stiffness
Renal and urinary disorders: pollakiuria
Skin and subcutaneous disorder: miliaria
Chronic Rhinosinusitis with Nasal Polyps
The safety of NUCALA has been studied in a double-blind, randomized, placebo-controlled, multicentre, 52-week treatment trial. A total of 407 adult subjects with CRSwNP were evaluated. Subjects received 100 mg of NUCALA or placebo subcutaneously once every 4 weeks. Adverse events from this study that were reported by 3% or more of patients treated with NUCALA 100 mg SC and that were reported more frequently than placebo (≥1% difference from placebo) are presented in Table 4.
Table 4 On-treatment Adverse Events with ≥3% incidence with NUCALA 100 mg SC and ≥1% more common with NUCALA than placebo in adult subjects with CRSwNP
| Adverse Events1 | NUCALA 100 mg SC (N =206) n (%) | Placebo (N = 201) n (%) |
|---|---|---|
| Gastrointestinal disorders | ||
| Abdominal pain upper | 7 (3%) | 5 (2%) |
| Diarrhea | 6 (3%) | 4 (2%) |
| Infections and infestations | ||
| Nasopharyngitis | 52 (25%) | 46 (23%) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 13 (6%) | 5 (2%) |
| Respiratory, thoracic and mediastinal disorders | ||
| Oropharyngeal pain | 16 (8%) | 10 (5%) |
| Nasal Dryness | 6 (3%) | 1 (<1%) |
| General disorders and administration site conditions | ||
| Pyrexia | 6 (3%) | 5 (2%) |
| Skin and subcutaneous tissue disorders | ||
| Rash | 6 (3%) | 2 (<1%) |
1 MedDRA Version 22.1
No additional adverse drug reactions (events considered to be possibly related to treatment with NUCALA 100 mg SC) were identified to those reported in the severe asthma trials.
Fatalities
No fatal serious adverse events were reported during the 52-week treatment period of study 205687.
Serious Adverse Events
On-treatment serious adverse events from placebo-controlled study 205687 were reported in 6% of subjects receiving NUCALA 100mg SC and 6% of subjects receiving placebo.
Adverse Events of Special Interest
Systemic Reactions: In study 205687, the percentage of patients who experienced systemic (allergic [type I hypersensitivity] and other) reactions was <1% in the group receiving NUCALA 100 mg and <1% in the placebo group. Systemic allergic (type I hypersensitivity) reactions were reported in 2 patients (<1%) in the group receiving NUCALA 100 mg and no patients in the placebo group. The manifestations of systemic allergic (type I hypersensitivity) reactions included urticaria, erythema, and rash and 1 of the 3 reactions occurred on the day of dosing. Other systemic reactions were reported by no patients in the group receiving NUCALA 100 mg and <1% of patients in the placebo group.
Injection Site Reaction: Injection site reactions occurred at a rate of 2% in patients receiving NUCALA 100 mg compared with <1% in patients receiving placebo. Common symptoms included erythema/redness and itching/pruritus.
Less Common Clinical Trial Adverse Reactions in Subjects with CRSwNP
In addition to the events shown in Table 4, adverse events reported less commonly (defined as <3% in the ‘mepolizumab’ treatment group) from the placebo-controlled 205687 clinical trial and were reported in 2 or more patients receiving NUCALA compared to no reports in patients receiving placebo are summarized below.
Blood and lymphatic disorders: anemia
Gastrointestinal disorders: abdominal discomfort, gastritis erosive
General disorders and administration site conditions: oedema peripheral
Infections and infestations: conjunctivitis, hordeolum, oral candidiasis, otitis media chronic
Musculoskeletal and connective tissue disorders: intervertebral disc protrusion
Neoplasms: skin papilloma
Nervous system disorders: facial paralysis, hyposmia, paraesthesia
Reproductive system and breast disorders: uterine polyp
Respiratory, thoracic and mediastinal disorders: rhinitis allergic, dyspnea
Skin and subcutaneous disorder: erythema
Chronic Obstructive Pulmonary Disease
The safety of NUCALA has been studied in 3 randomized, double-blind, placebo-controlled, multicenter trials of 52 to 104 weeks duration. A total of 2089 subjects with COPD who received 100 mg of NUCALA or placebo subcutaneously once every 4 weeks were evaluated. Adverse events from these studies that were reported by 1% or more of subjects treated with NUCALA 100 mg SC and that were reported more frequently than placebo (≥1% difference from placebo) are presented in Table 5.
Table 5 On-treatment Adverse Events with ≥1% incidence with NUCALA 100 mg SC and ≥1% more common with NUCALA than placebo in adult subjects with COPD from placebo-controlled studies (208657, MEA117113 and MEA117106)
| Adverse Events1 | NUCALA 100 mg SC (N = 1043) n (%) | Placebo (N = 1046) n (%) |
|---|---|---|
| Gastrointestinal disorders | ||
| Diarrhea | 56 (5%) | 41 (4%) |
| Respiratory, thoracic and mediastinal disorders | ||
| Oropharyngeal pain | 46 (4%) | 26 (3%) |
| Infections and infestations | ||
| Urinary tract infection | 42 (4%) | 29 (3%) |
1 MedDRA Version 27
Fatalities
In the three placebo-controlled studies that included patients with COPD, 31 subjects (3%) receiving NUCALA 100 mg SC and 37 subjects (4%) receiving placebo died due to fatal serious adverse events (on- and post-treatment). Fatal serious adverse events reported in ≥5 subjects across the two treatment groups were COPD exacerbation (8 subjects receiving NUCALA 100 mg SC and 8 subjects receiving placebo) and cardiac arrest (3 subjects receiving NUCALA 100 mg SC and 2 subjects receiving placebo).
Serious Adverse Events
In the three placebo-controlled COPD studies, serious adverse events (on-treatment) were reported in 24% of subjects receiving NUCALA 100 mg SC and 27% of subjects receiving placebo. The most common on-treatment serious adverse events were COPD exacerbation, pneumonia, and respiratory failure.
Adverse events leading to withdrawal from clinical trials
In the 3 placebo-controlled studies in COPD, 3% of subjects receiving NUCALA 100 mg SC, and 4% of subjects in the placebo group withdrew due to an on-treatment adverse event. The most frequently reported on-treatment adverse events leading to withdrawal in subjects receiving NUCALA 100 mg SC were COPD (6 subjects), cardiac arrest (4 subjects), COVID-19 (3 subjects), pneumonia (2 subjects), sepsis (2 subjects) and anaemia (2 subjects).
Adverse Events of Special Interest
Systemic Reactions: In a 52 to 104-week placebo-controlled COPD study, systemic allergic (type I hypersensitivity) reactions were reported in 1 of 403 patients (<1%) receiving NUCALA 100 mg SC and no patients in the placebo group (401 patients). Other systemic reactions were reported by 4 patients (<1%) receiving NUCALA 100 mg SC and in 4 patients (<1%) in the placebo groups.
In two 52-week placebo-controlled COPD studies, systemic allergic/hypersensitivity reactions were reported in 4 of 640 patients (<1%) receiving NUCALA 100 mg SC and in 3 of 645 patients (<1%) in the placebo group. Systemic non-allergic reactions were reported by 7 patients (1%) receiving NUCALA 100 mg SC and in 10 patients (2%) in the placebo group.
Infections: In the 3 pooled COPD studies, overall infections were reported with similar frequency in the NUCALA 100 mg SC (49%) and the placebo treatment groups (49%). The most frequently reported on treatment infection was nasopharyngitis in both the NUCALA 100 mg SC group (14%, 144/1043) and the placebo group (14%, 143/1046). No parasitic infection adverse events were reported in the 3 pooled COPD studies.
Serious infections were reported by 9% in both the NUCALA 100 mg SC group and the placebo group, with pneumonia being the most frequently reported serious infection (5% NUCALA 100 mg group, 5% in the placebo group). Five subjects (<1%) with on- and post-treatment fatal serious adverse events were reported for the NUCALA 100 mg SC group (COVID-19 and sepsis for 3 and 2 subjects, respectively), and 7 subjects (<1%) in the placebo group (pneumonia for 4 participants, COVID-19, infective exacerbation of chronic obstructive airways disease and urinary tract infection for 1 participant each).
In the 3 pooled COPD studies, reporting of potential opportunistic infections were similar in the NUCALA 100 mg SC group (2%) and the placebo group (1%). Herpes zoster was the most frequently reported event, both in the NUCALA 100 mg SC (1%, 14 of 1043 participants) group and the placebo group (<1%, 7/1046). One opportunistic infection in each treatment group was reported by the investigator to be related to study treatment. All events resolved with continued treatment except for 1 participant in the placebo group.
Cardiovascular Events: In the 3 pooled COPD studies, on-treatment cardiac events were reported in 8% of subjects in the NUCALA 100 mg SC group, and 9% in the placebo group. The most frequently reported on-treatment AE was atrial fibrillation (2% subjects in the NUCALA 100 mg SC group and 2% subjects in the placebo group).
On- and post-treatment fatal cardiac serious adverse events were reported in 10 (<1%) of subjects in the NUCALA 100 mg SC group, and 4 (<1%) of subjects in the placebo group in the 3 pooled COPD studies.
Injection Site Reactions: Injection site reactions (e.g., erythema, hematoma, swelling, pruritus) occurred in 2% of subjects in both NUCALA 100 mg SC and placebo treatment groups.
Neoplasms and Malignancies: In the 3 pooled COPD studies, neoplasms were reported in 3% of subjects in the NUCALA 100 mg SC group, and 4% in the placebo group.
Malignancies were reported in 2% of participants each in the NUCALA 100 mg SC and placebo groups. The types of on-treatment adverse events of malignancies reported were those that are common in the general population. Each type of malignancy was reported by <1% of participants in both groups. The most frequently reported adverse event across treatment groups was lung neoplasm malignant (3 participants in the NUCALA 100 mg SC group, 2 participants in the placebo group). No malignancies were reported by the investigator to be related to study treatment.
Less Common Clinical Trial Adverse Reactions in Subjects with COPD
In addition to the events shown in Table 5, adverse events reported less commonly (defined as <1% in the NUCALA 100 mg SC group) from the 3 placebo-controlled clinical trials in adults and were reported in 3 or more subjects receiving NUCALA compared to no reports in patients receiving placebo are summarized below.
Gastrointestinal disorders: hemorrhoidal hemorrhage
General disorders and administration site conditions: facial pain
Infections and Infestations: pulpitis dental
Investigations: hemoglobin decreased
Skin and subcutaneous disorder: skin lesion
Eosinophilic Granulomatosis with Polyangiitis
The safety of NUCALA has been studied in a double-blind, randomized, placebo-controlled, multicentre, 52-week treatment trial. A total of 136 subjects with EGPA were evaluated. Subjects received 300 mg of NUCALA or placebo subcutaneously once every 4 weeks. Adverse events from this study that were reported by 5% or more of patients treated with NUCALA 300 mg SC and that were reported more frequently than placebo (≥1% difference from placebo) are presented in Table 6.
Table 6 On-treatment Adverse Events with ≥5% incidence with NUCALA and ≥1% more common with NUCALA than placebo in subjects with EGPA
| Adverse Events1 | NUCALA 300 mg SC (N =68) n (%) | Placebo (N = 68) n (%) |
|---|---|---|
| Ear and labyrinth disorders | ||
| Vertigo | 5 (7%) | 1 (1%) |
| Eye disorders | ||
| Vision blurred | 4 (6%) | 2 (3%) |
| Gastrointestinal disorders | ||
| Diarrhea | 12 (18%) | 8 (12%) |
| Vomiting | 11 (16%) | 4 (6%) |
| General disorders and administration site conditions | ||
| Injection site reaction2 | 9 (13%) | 7 (10%) |
| Asthenia | 5 (7%) | 3 (4%) |
| Infections and infestations | ||
| Sinusitis | 14 (21%) | 11 (16%) |
| Upper respiratory tract infection | 14 (21%) | 11 (16%) |
| Urinary tract infection | 5 (7%) | 4 (6%) |
| Acute sinusitis | 6 (9%) | 2 (3%) |
| Rhinitis | 5 (7%) | 3 (4%) |
| Fungal skin infection | 4 (6%) | 3 (4%) |
| Gastroenteritis | 5 (7%) | 2 (3%) |
| Oral herpes | 4 (6%) | 3 (4%) |
| Investigations | ||
| Alanine aminotransferase increased | 5 (7%) | 0 |
| Weight increased | 4 (6%) | 1 (1%) |
| Injury, poisoning and procedural complications | ||
| Ligament sprain | 4 (6%) | 1 (1%) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 15 (22%) | 12 (18%) |
| Back pain | 9 (13%) | 6 (9%) |
| Neck pain | 8 (12%) | 2 (3%) |
| Musculoskeletal pain | 6 (9%) | 2 (3%) |
| Nervous system disorders | ||
| Headache | 22 (32%) | 12 (18%) |
| Paraesthesia | 4 (6%) | 3 (4%) |
| Respiratory, thoracic and mediastinal disorders | ||
| Oropharyngeal pain | 8 (12%) | 5 (7%) |
| Skin and subcutaneous tissue disorders | ||
| Rash | 9 (13%) | 6 (9%) |
| Pruritus | 6 (9%) | 1 (1%) |
| Urticaria | 4 (6%) | 1 (1%) |
1 MedDRA Version 19.0
2 The most common symptoms associated with subcutaneous injections included: erythema, bruising, pain, swelling, and warm to touch.
No additional adverse drug reactions (events considered to be possibly related to treatment with mepolizumab) were identified to those reported in the severe asthma trials.
Fatalities
In clinical studies that included patients with EGPA, 2 subjects receiving NUCALA died (fatal cardiac arrest in both cases). One death occurred in an open-label long-term access program containing subjects that participated in the placebo-controlled trial. Neither death was considered related to study medication by the investigators.
Serious Adverse Events
Serious adverse events were reported in 18% of subjects receiving NUCALA and 26% of subjects receiving placebo.
Adverse Events leading to withdrawal from clinical trial
Two subjects (3%) receiving NUCALA and 1 (1%) subject receiving placebo withdrew due to an adverse event. Adverse events leading to withdrawal in subjects receiving NUCALA included cardiac arrest (1 subject) and hypersensitivity (1 subject). Adverse events leading to withdrawal in subjects receiving placebo included pneumonia (1 subject).
Adverse Events of Special Interest
Systemic Allergic Reactions: Systemic hypersensitivity reactions were reported in 4% of subjects that received NUCALA and in 1% of subjects that received placebo. One subject receiving NUCALA reported a hypersensitivity reaction that was serious and severe but was not considered anaphylaxis. Symptoms associated with this reaction included malaise, hypertension, chills, pallor, cold extremities, warm sensation in trunk and neck, dyspnea, and stridor. Two of the four reported events of hypersensitivity occurred on the day of dosing.
Infections: Overall infections were reported with similar frequency in the NUCALA (84%) and placebo (78%) treatment groups. Serious infections were reported in 6% of subjects in the NUCALA treatment group and 15% of subjects in the placebo treatment group. Events considered to represent potential opportunistic infections were reported in 7% of subjects receiving NUCALA and in 3% of subjects in the placebo group.
Cardiovascular Events: Cardiac events were reported in 6% of subjects that received NUCALA and 9% subjects that received placebo. Serious cardiac events were reported in 1% of subjects in the NUCALA treatment group and 3% of subjects in the placebo treatment group.
Injection Site Reaction: Injection site reactions were reported at a rate of 15% in subjects treated with NUCALA compared with 13% in subjects treated with placebo. Common symptoms included erythema, bruising, pain, swelling, and warm to touch.
Neoplasms and Malignancies: Neoplasms were reported in 1% of subjects in the NUCALA group and 4% of subjects in the placebo group. Malignancies were reported in no subjects receiving NUCALA and 2 subjects (3%) in the placebo group.
Less Common Clinical Trial Adverse Reactions in Subjects with EGPA
In addition to the events shown in Table 6, adverse events reported less commonly (defined as <5% in the ‘mepolizumab’ treatment group) from the placebo-controlled MEA115921 clinical trial and were reported in 2 or more patients receiving NUCALA compared to no reports in patients receiving placebo are summarized below.
Blood and lymphatic disorders: anemia
Ear and labyrinth disorders: deafness, tinnitus
Endocrine disorders: adrenal insufficiency, steroid withdrawal syndrome
Eye disorders: eye pruritic, eye pain
Gastrointestinal disorder: hemorrhoids
Immune system disorders: food allergy
Infections and infestations: candida infection, herpes simplex, pharyngitis, influenza like illness
Injury, poisoning and procedural complications: muscle strain, skin abrasion
Investigations: aspartate aminotransferase increased, gamma-glutamyltransferase increased
Musculoskeletal and connective tissue disorders: bursitis
Respiratory, thoracic and mediastinal disorders: nasal polyps, pulmonary pain, rhinitis allergic
Skin and subcutaneous disorder: skin lesion, rash pruritic
Vascular disorders: hot flush
Hypereosinophilic Syndrome
The safety of NUCALA has been studied in a double-blind, randomized, placebo-controlled, multicentre, 32-week treatment trial. A total of 108 subjects with HES were evaluated. Subjects received 300 mg of NUCALA or placebo subcutaneously once every 4 weeks. Adverse events from this study that were reported by 5% or more of patients treated with NUCALA 300 mg SC and that were reported more frequently than placebo (≥1% difference from placebo) are presented in Table 7.
Table 7 On-treatment Adverse Events with ≥5% incidence with NUCALA 300 mg SC and ≥1% more common with NUCALA than placebo in subjects with HES
| Adverse Events1 | NUCALA 300 mg SC (N =54) n (%) | Placebo (N = 54) n (%) |
|---|---|---|
| Gastrointestinal disorders | ||
| Vomiting | 4 (7%) | 3 (6%) |
| Nausea | 3 (6%) | 2 (4%) |
| Constipation | 3 (6%) | 1 (2%) |
| General disorders and administration site conditions | ||
| Pyrexia | 4 (7%) | 2 (4%) |
| Influenza like illness | 3 (6%) | 2 (4%) |
| Injection site reaction2 | 3 (6%) | 2 (4%) |
| Infections and infestations | ||
| Upper respiratory tract infection | 8 (15%) | 2 (4%) |
| Urinary tract infection | 5 (9%) | 0 |
| Influenza | 3 (6%) | 1 (2%) |
| Injury, poisoning and procedural complications | ||
| Contusion | 4 (7%) | 1 (2%) |
| Musculoskeletal and connective tissue disorders | ||
| Pain in extremity | 6 (11%) | 2 (4%) |
| Myalgia | 4 (7%) | 3 (6%) |
| Musculoskeletal chest pain | 3 (6%) | 0 |
| Nervous system disorders | ||
| Dizziness | 4 (7%) | 3 (6%) |
| Hypoaesthesia | 3 (6%) | 1 (2%) |
| Paraesthesia | 3 (6%) | 0 |
| Reproductive system and breast disorders | ||
| Vaginal haemorrhage | 3 (6%) | 0 |
| Respiratory, thoracic and mediastinal disorders | ||
| Dyspnoea | 3 (6%) | 2 (4%) |
| Nasal obstruction | 3 (6%) | 2 (4%) |
| Skin and subcutaneous tissue disorders | ||
| Alopecia | 4 (7%) | 0 |
1 MedDRA Version 22.0
2 The symptoms associated with subcutaneous injections were reported as burning, hematoma, pruritis and rash.
No additional adverse drug reactions (events considered to be possibly related to treatment with mepolizumab) were identified to those reported in the severe asthma trials.
Following the pivotal placebo-controlled, 32-week study (study 200622), in patients who tolerated NUCALA 300 mg SC (or who switched from placebo) and who agreed to continue into a 20 week open label extension study (study 205203), the safety profile of NUCALA in HES patients (n=102) was similar.
Fatalities
In two placebo-controlled clinical studies (study 200622 with NUCALA SC 300 mg and another study with mepolizumab IV 750 mg), 2/97 subjects receiving NUCALA died (fatal HES flare, pneumonia, respiratory failure, and septic shock for one subject [NUCALA SC 300 mg], and fatal cardiac arrest for the other subject [mepolizumab IV 750 mg]). Neither death was considered related to study medication by the investigators.
Serious Adverse Events
Serious adverse events from the two placebo-controlled studies were reported in 18% of subjects receiving NUCALA and 14% of subjects receiving placebo.
Adverse Events of Special Interest
Systemic Allergic Reactions: No systemic allergic (type I hypersensitivity) reactions were reported in study 200622. Other systemic reactions were reported by 1 (2%) patient in the group receiving 300 mg of NUCALA (multifocal skin reaction on the day of dosing) and no patients in the placebo group.
Injection Site Reaction: Injection site reactions were reported at a rate of 7% in subjects treated with NUCALA 300 mg SC in study 200622, compared with 4% in subjects treated with placebo. Common symptoms included erythema, bruising, pain, swelling, and warm to touch.
Less Common Clinical Trial Adverse Reactions in Subjects with HES
In addition to the events shown in Table 7, adverse events reported less commonly (defined as <5% in the ‘mepolizumab’ treatment group) from the placebo-controlled 200622 clinical trial and were reported in 2 or more patients receiving NUCALA compared to no reports in patients receiving placebo are summarized below.
Cardiac disorders: palpitations
Ear and labyrinth disorders: tinnitus
General disorders and administration site conditions: malaise
Infections and infestations: erysipelas, respiratory tract infection, tooth infection
Injury, poisoning and procedural complications: skin abrasion
Skin and subcutaneous disorder: hyperhidrosis
8.3. Less Common Clinical Trial Adverse Reactions
See Section 8.2 Clinical Trial Adverse Reactions.
8.5. Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of NUCALA:
Immune System Disorders: Hypersensitivity reactions including anaphylaxis.
9. Drug Interactions
9.2. Drug Interactions Overview
No formal interaction studies have been performed with NUCALA.
9.4. Drug-Drug Interactions
Interactions with other drugs have not been formally studied.
9.5. Drug-Food Interactions
Interactions with food have not been studied.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been studied.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Mepolizumab is a targeted anti-interleukin-5 (IL-5) IgG1 kappa monoclonal antibody. IL-5 is one of the cytokines involved in eosinophilic inflammation and is responsible for the growth and differentiation, recruitment, activation, and survival of eosinophils. Mepolizumab binds to soluble IL-5 with high affinity (a dissociation constant of 100 pM), preventing IL-5 from binding to the alpha chain of the IL-5 receptor complex expressed on the eosinophil cell surface, thereby reducing the production and survival of eosinophils. Inflammation is an important component in the pathogenesis of asthma, CRSwNP, COPD, EGPA and HES. The reduction of eosinophilic inflammation may play an important role in eliciting a therapeutic effect in the treatment of these diseases; however, the precise mechanism of mepolizumab action has not been definitively established.
10.2. Pharmacodynamics
Severe Eosinophilic Asthma: Following treatment with mepolizumab, dose-dependent pharmacodynamic responses, i.e. reductions in blood eosinophil levels from baseline, were observed in adult asthma patients with mean baseline blood eosinophil levels greater than 300 cells/mcL (ranged 150 – 2420 cells/mcL). Subjects were assigned to receive one of four mepolizumab treatments (administered every 4 weeks for a total of three doses): 12.5 mg SC, 125 mg SC, 250 mg SC, or 75 mg IV. Sixty-six (66) of the 70 randomized subjects completed the trial. A reduction in blood eosinophil levels was observed in all treatment groups by Day 3. On Day 84 (4 weeks post-last dose), model-estimated inhibition of blood eosinophils was 57% (95% CI: 42, 69), 86% (95% CI: 83, 88), 86% (95% CI: 83, 89), and 88% (95% CI: 85, 90) in the 12.5 mg SC, 75 mg IV, 125 mg SC, and 250 mg SC treatment groups, respectively. The SC model-estimated doses to provide 50% and 90% of maximal inhibition of blood eosinophils at Day 84 were 11 and 99 mg, respectively.
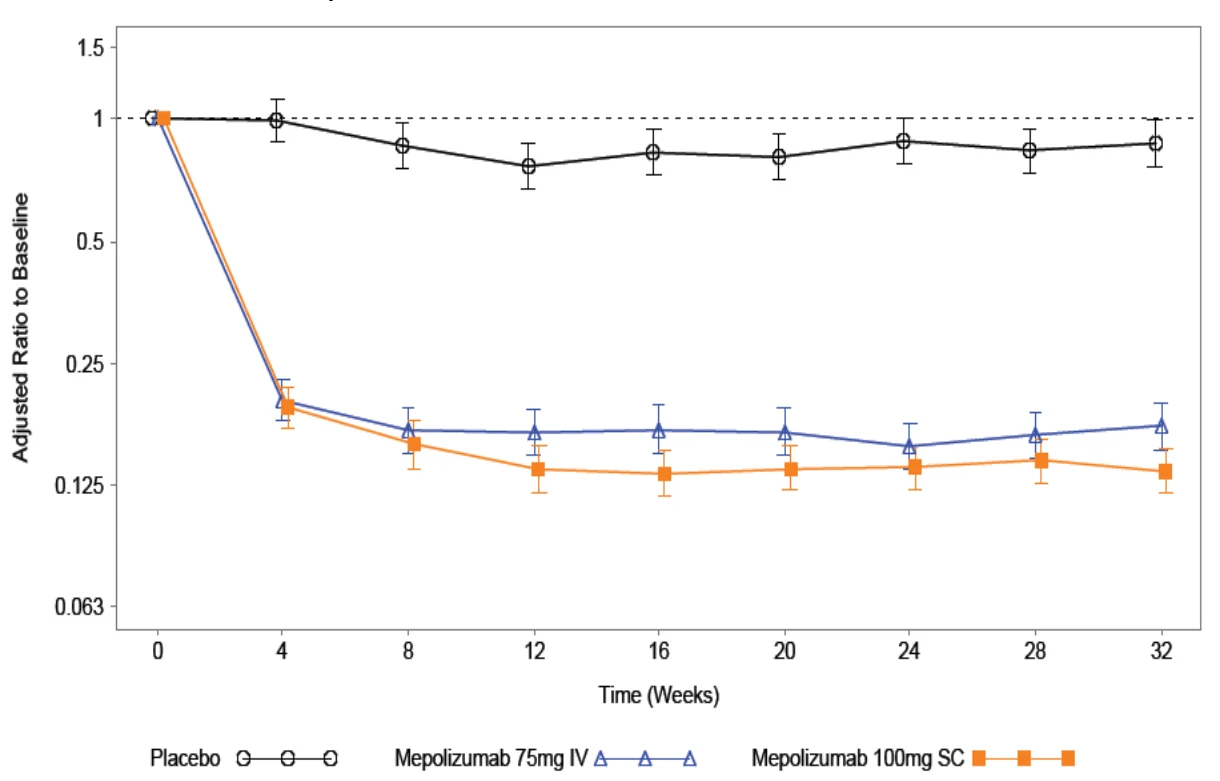
In adults and adolescents, following SC administration of mepolizumab 100 mg every 4 weeks for 32 weeks, blood eosinophils were reduced to a geometric mean count of 40 cells/mcL, which corresponds to a geometric mean reduction of 84% compared with placebo. Consistent results were observed following mepolizumab IV administration at 75 mg and SC administration at 100 mg (Figure 1). The magnitude of blood eosinophil reduction in a select subset of adult and adolescent subjects with severe eosinophilic asthma (n=998) who were tolerant to NUCALA and entered the open-label, uncontrolled, extension studies and were treated with NUCALA 100 mg SC for a median of 2.8 years (range 4 weeks to 4.5 years) was consistent with that observed in the placebo-controlled studies.
In children (n = 29), following either mepolizumab 40 mg (for a weight < 40 kg) or 100 mg (for a weight ≥ 40 kg) administered subcutaneously every 4 weeks for 52 weeks, blood eosinophils were reduced to a geometric mean count of 48 cells/mcL (85% reduction from baseline) and 44 cells/mcL (87% reduction from baseline), respectively.
In adults, adolescents, and children, the magnitude of reduction was observed at the first post-dose measurement interval (4 weeks) and was maintained throughout the treatment period.
Figure 1 Reduction in blood eosinophils from baseline over 32 weeks (MENSA in adults and adolescents)
Chronic Rhinosinusitis with Nasal Polyps: Following SC administration of mepolizumab 100 mg every 4 weeks for 52 weeks in subjects with CRSwNP, blood eosinophils were reduced to a geometric mean count of 60 cells/mcL. This equates to a geometric mean reduction of 81% at Week 4 compared to placebo which was maintained at 83% at Week 52.
Chronic Obstructive Pulmonary Disease: Following SC administration of mepolizumab 100 mg every 4 weeks for 52 to 104 weeks in subjects with COPD, blood eosinophils were reduced to a geometric mean count of 60 cells/mcL. This corresponds to a geometric mean reduction of 79% at Week 52 and 80% at Week 104 compared to placebo.
Eosinophilic Granulomatosis with Polyangiitis: Following SC administration of mepolizumab 300 mg every 4 weeks for 52 weeks in subjects with EGPA, blood eosinophils were reduced to a geometric mean count of 38 cells/mcL. There was a geometric mean reduction of 83% compared to placebo and this magnitude of reduction was observed within 4 weeks of treatment.
Hypereosinophilic Syndrome: Following SC administration of mepolizumab 300 mg every 4 weeks for 32 weeks in subjects with HES, blood eosinophils were reduced to a geometric mean count of 70 cells/mcL and a geometric mean reduction of 92% compared to placebo was observed and this magnitude of reduction was observed within 2 weeks of treatment. This magnitude of reduction was similar following a 20 week open-label extension study in patients that continued mepolizumab treatment.
10.3. Pharmacokinetics
Following SC dosing in subjects with moderate/severe asthma, mepolizumab exhibited approximately dose-proportional pharmacokinetics over a dose range of 12.5 mg to 250 mg.
In population pharmacokinetic analysis, the pharmacokinetics of mepolizumab in subjects with CRSwNP or COPD dosed at 100 mg SC is consistent with that reported in subjects with asthma.
In population pharmacokinetic analysis, the pharmacokinetics of mepolizumab in subjects with EGPA or HES dosed at 300 mg SC is consistent with that reported in subjects with asthma. Systemic exposure following administration of mepolizumab 300 mg SC in subjects with EGPA or HES was approximately 3 times that of mepolizumab 100 mg administered SC in subjects with severe asthma.
Table 8 Summary of simulated steady-state mepolizumab pharmacokinetic parameters after subcutaneous administration across mepolizumab indications
| Dose Regimen (Condition) | Cmaxss1 [mcg/mL] | Cavgss1 [mcg/mL] | AUC4wks,SS1 [mcg*day/mL] | t ½1 [days] | CL2 [L/day] | Tmax3 [day] | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 100 mg q4w (Asthma) | 17.40 (5.11) | 12.96 (4.43) | 363.0 (124.1) | N/C | 0.288 (0.112) | 4-7 | ||||||
| 100 mg q4w (CRSwNP) | N/C | 12.87 (4.13) | 360.3 (115.6) | 23.00 (5.23) | 0.230 (0.075) | |||||||
| 100 mg q4w (COPD) | 17.62 (5.61) | 12.00 (4.55) | 336.1 (127.3) | 22.02 (8.05) | 0.232 (0.082) | |||||||
| 300 mg q4w (EGPA) | 54.29 (14.24) | 43.43 (12.15) | 1216 (340.1) | 24.94 (4.89) | 0.201 (0.059) | |||||||
| 300 mg q4w (HES) | N/C | 35.46 (12.69) | 992.9 (355.3) | 19.99 (3.88) | 0.264 (0.116) | |||||||
Data presented as mean (SD) except for Tmax which is range of median.
1 Simulated mepolizumab exposures from population PK analysis.
2 Parameter based on population PK analysis.
3 Tmax is directly observed from Asthma and EGPA populations and is typical of absorption of mAbs from SC administration.
Area under the curve (AUC4 weeks, ss) at steady state over 4 weeks and the maximum concentration at steady state (Cmax) following administration of mepolizumab.
N/C = not calculated
Following a single 100 mg SC administration in healthy subjects, mepolizumab systemic exposure was comparable between formulations.
Absorption:
Following SC administration to healthy subjects or patients with asthma, mepolizumab was absorbed slowly with a median time to reach maximum plasma concentration (Tmax) ranging from 4 to 8 days.
Following a single 250 mg subcutaneous administration in the abdomen, thigh or arm of healthy subjects, mepolizumab absolute bioavailability was 64%, 71% and 75%, respectively. In patients with asthma, the absolute bioavailability of mepolizumab administered SC in the arm ranged from 74%-80%.
Following repeat SC administration every 4 weeks, steady-state is reached by 16 weeks and there is approximately a two-fold accumulation at steady state.
Distribution:
Following a single IV administration of mepolizumab to patients with asthma, the mean volume of distribution is 55 to 85 mL/kg.
Metabolism:
Mepolizumab is a humanized IgG1 monoclonal antibody degraded by proteolytic enzymes which are widely distributed in the body and not restricted to hepatic tissue.
Elimination:
Following SC administration of mepolizumab, the mean terminal half-life (t1/2) ranged from 16 to 22 days. In a population pharmacokinetic analysis, the estimated mepolizumab systemic clearance was 3.1 mL/day/kg.
Special Populations and Conditions
Pediatrics (6 to 11 years of age): Mepolizumab pharmacokinetics following SC administration in subjects 6 to 11 years of age with severe eosinophilic asthma (n = 36) was investigated in the 12-week treatment phase of the uncontrolled, open-label study (200363). Exposures (as
- measured by AUC) following SC administration of either 40 mg (for a weight < 40 kg) or 100 mg (for a weight ≥ 40 kg) were 1.32 and 1.97 times of that observed in adults and adolescents administered 100 mg. Based on a population pharmacokinetic model updated by these results, simulation of a 40 mg SC dose every 4 weeks in children, irrespective of weight, resulted in predicted exposures similar to those observed in adults and adolescents.
- Geriatrics (≥ 65 years of age): No formal studies have been conducted to investigate the pharmacokinetics of mepolizumab in elderly patients. However, in the population pharmacokinetic analysis, there were no indications of an effect of age (range included 12-82 years) on the pharmacokinetics of mepolizumab.
- Ethnic Origin: A population pharmacokinetics analysis of mepolizumab data indicated that there was no significant effect of race and gender on mepolizumab clearance.
- Hepatic Insufficiency: No formal studies have been conducted to investigate the effect of hepatic impairment on the pharmacokinetics of mepolizumab. Since mepolizumab is degraded by widely distributed proteolytic enzymes, not restricted to hepatic tissue, changes in hepatic function are unlikely to have any effect on the elimination of mepolizumab.
- Renal Insufficiency: No formal studies have been conducted to investigate the effect of renal impairment on the pharmacokinetics of mepolizumab. Based on population pharmacokinetic analyses, mepolizumab clearance was comparable between patients with creatinine clearance values between 50-80 mL/min and patients with normal renal function. There are limited data available in patients with creatinine clearance values <50 mL/min; however, mepolizumab is not cleared renally.
10.4. Immunogenicity
All therapeutic proteins have the potential for immunogenicity.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
In placebo-controlled clinical studies that enrolled adults and adolescents with severe eosinophilic asthma treated with NUCALA 100 mg SC over 24 to 32 weeks, 6% (15/260) subjects had detectable anti-mepolizumab antibodies (Studies MEA115588, MEA115575). Neutralizing antibodies were detected in one adult subject receiving NUCALA. In an open label extension study in adult and adolescent subjects with severe eosinophilic asthma (n=998) who were tolerant to NUCALA 100 mg SC; 6% (60/992) subjects had detectable anti-mepolizumab antibodies. This was consistent with the immunogenicity incidence observed in the placebo-controlled studies. All subjects were negative for neutralizing antibodies. In children with severe eosinophilic asthma treated with NUCALA 40 or 100 mg SC over 12 weeks and 52 weeks, 6% (2/35) and 0% (0/30) had detectable anti-mepolizumab antibodies (placebo-controlled Study 200363 Part A and open label extension Part B, respectively). All subjects were negative for neutralizing antibodies.
In subjects with CRSwNP treated with NUCALA 100 mg SC over 52 weeks, 3% (6/196) had detectable anti-mepolizumab antibodies (placebo control Study 205687).
In subjects with COPD treated with NUCALA 100 mg SC over 52 to 104 weeks, 3% (34/990) had detectable anti-mepolizumab antibodies (placebo-controlled Studies MEA117106, MEA117113, and 208657 with an open label extension).
In subjects with EGPA treated with NUCALA 300 mg SC over 52 weeks, 1% (1/68) had detectable anti-mepolizumab antibodies (placebo-controlled Study MEA115921).
In subjects with HES treated with NUCALA 300 mg SC over 32 weeks and a 20-week open label extension, 2% (1/53) and 0% (0/102) had detectable anti-mepolizumab antibodies (Studies 200622 and 205203, respectively).
No neutralizing antibodies were detected in subjects with CRSwNP, COPD, EGPA, and HES.
Overall, the clinical impact of the presence of anti-mepolizumab antibodies is not known.
- 11. Storage, Stability, and Disposal
Lyophilized powder
Unopened vial
Store in the original carton below 25°C until use. Do not freeze. Protect from light.
Reconstituted solution
After reconstitution with Water for Injection, the product is stable for up to 8 hours when stored below 30°C. Do not freeze. During administration, protection from light is not necessary. Any unused concentrate or solution remaining after 8 hours must be discarded.
Solution in pre-filled autoinjector or pre-filled syringe (safety syringe)
Store in the original carton to protect from light. The pre-filled autoinjector or pre-filled syringe should be stored refrigerated (2°C to 8°C), but if necessary can be removed from the refrigerator and kept in the unopened carton for up to 7 days at below 30°C, when protected from light. Do not freeze. Discard if unopened carton is left out of the refrigerator for more than 7 days.
The pre-filled autoinjector or pre-filled syringe must be administered within 8 hours once the carton is opened. Discard if not administered within 8 hours.
12. Special Handling Instructions
Do not mix the reconstituted NUCALA solution for injection with other medicinal products.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: Mepolizumab
Chemical name: Not applicable. Mepolizumab is not a chemical. It is an immunoglobulin (recombinant human IgG1 monoclonal antibody)
Molecular formula and molecular mass: C6476H10084N1732O2028S46 (without oligosaccharide). The polypeptide molecular mass is 146 kDa and the carbohydrate molecular mass is approximately 3 kDa resulting in a total estimated molecular mass of 149 kDa for mepolizumab.
Structural formula: Mepolizumab is a humanized IgG1 kappa immunoglobulin and consists of two heavy chains of 449 amino acids and two light chains of 220 amino acids. The heavy and light chains are covalently linked by a single disulfide bond and the heavy chains are linked to each other by two disulfide bonds resulting in a typical IgG molecule.
Physicochemical properties: Mepolizumab is a clear to opalescent, colourless to pale yellow or pale brown solution.
Product Characteristics:
Mepolizumab is a humanized monoclonal antibody (IgG1, kappa) produced by recombinant DNA technology in Chinese Hamster Ovary (CHO) cells. Mepolizumab is expressed as a soluble glycoprotein secreted into an animal component free cell culture medium, purified and formulated to produce bulk drug substance (BDS).
14. Clinical Trials
14.1. Clinical Trials by Indication
Severe Eosinophilic Asthma
The efficacy and safety of adjunctive mepolizumab treatment in severe eosinophilic asthma was evaluated in two phase III, randomized, double-blind, parallel-group clinical trials of 24 to 32 weeks’ duration in 711 subjects aged 12 years and older, including 27 adolescents (Table 9).
- Exacerbation trial (MENSA) – 75 mg IV or 100 mg SC vs. placebo
- Oral corticosteroid (OCS) reduction trial (SIRIUS) – 100 mg SC vs. placebo
These clinical trials were designed to evaluate the efficacy and safety of mepolizumab administered once every 4 weeks in subjects with severe eosinophilic asthma not adequately controlled on high-dose inhaled corticosteroid (ICS) (an equivalent of ≥1000 mcg fluticasone propionate/day for subjects 18 years of age and older) or medium-dose ICS (an equivalent of ≥500 mcg fluticasone propionate/day for subjects 12 to 17 years of age) and an additional controller(s) (e.g., long-acting beta-agonist (LABA), leukotriene receptor antagonist (LTRA), and/or theophylline) with or without oral corticosteroids (OCS)). In SIRIUS, all subjects were required to be on regular maintenance treatment with OCS.
An open-label, uncontrolled clinical trial evaluated the pharmacokinetics and pharmacodynamics (12 week duration) and safety (52 week duration) of mepolizumab treatment in 36 children (6 to 11 years of age) with severe eosinophilic asthma.
Table 9 Summary of Trial Designs in Severe Eosinophilic Asthma
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| MEA115588 (MENSA) | NUCALA 100 mg SC Mepolizumab 75 mg IV1 Placebo Duration: 32 weeks | n=194 n=191 n=191 Total: 576 | 50 years (12-82) | Female: 329 (57%) Male: 247 (43%) | |
| MEA115575 (SIRIUS) | 24-week, multicenter, randomized, double-blind, placebo-controlled, parallel group study of mepolizumab adjunctive therapy to reduce oral corticosteroid use in subjects with severe eosinophilic asthma | NUCALA 100 mg SC Placebo Duration: 24 weeks | n=69 n=66 Total: 135 | 50 years (16-74) | Female: 74 (55%) Male: 61 (45%) |
| 200363 | An open-label, uncontrolled, study to characterize the pharmacokinetics and pharmacodynamics of mepolizumab administered SC in children from 6 to 11 years of age with severe eosinophilic asthma | NUCALA 40 mg SC (for a weight < 40 kg) or NUCALA 100 mg SC (for a weight ≥ 40 kg) Duration: 12 weeks (short-term phase) 52 weeks (long-term phase) | n=36 n=30 | 8.6 years (5-12) 8.6 years (6-12) | Female: 11 (31%) Male: 25 (69%) Female: 10 (33%) Male: 20 (67%) |
IV = intravenous; SC = subcutaneous
1NUCALA is not indicated for intravenous use and should only be administered by the SC route.
MEpolizumab as adjunctive therapy iN patients with Severe Asthma (MENSA) Study
Study Design
MENSA was a 32-week, randomized, double-blind, parallel-group study evaluating the efficacy and safety of mepolizumab 75 mg IV or NUCALA 100 mg SC vs. placebo administered every four weeks in the add-on treatment of severe eosinophilic asthma in 576 subjects (Table 9). MENSA was the only pivotal exacerbation study to evaluate the direct effect of SC dosing on the exacerbation rate. The 100 mg SC and 75 mg IV doses were chosen to provide consistent systemic mepolizumab exposure and reduction of blood eosinophils over the treatment period (see 10.3 Pharmacokinetics).
Subjects had a history of two or more asthma exacerbations in the past 12 months despite regular use of high-dose ICS (or medium-dose ICS for adolescents) plus an additional controller(s) (e.g., LABA, LTRA, and/or theophylline) with or without OCS. Additionally, subjects had blood eosinophils of ≥150 cells/mcL (≥0.15 GI/L) at initiation (within 6 weeks of first dose) or blood eosinophils of ≥300 cells/mcL (≥0.3 GI/L) within 12 months of enrollment.
The primary endpoint was the frequency of clinically significant exacerbations of asthma, defined as worsening of asthma requiring use of oral/systemic corticosteroids and/or hospitalization and/or emergency room visits. For subjects on maintenance OCS, an exacerbation requiring OCS was defined as the use of oral/systemic corticosteroids at least double the existing maintenance dose for at least 3 days.
During the study, the percentage of patients who discontinued treatment and withdrew prematurely from the NUCALA 100 mg SC group, mepolizumab 75 mg IV group, and placebo group was 5%, 8% and 6%, respectively. The most common reason for discontinuation of treatment was patients withdrawing consent (3% overall).
Patient Demographics and Baseline Characteristics
Demographics and baseline characteristics were balanced between treatment groups (Table 10). During the trial, subjects continued their baseline asthma therapy, including high-dose ICS (or medium-dose ICS for adolescents), with an additional controller(s). Additionally, 24% of the subjects were on maintenance OCS (median 10.0 mg/day).
Table 10 Summary of Patient Demographics and Baseline Characteristics
NUCALA 100 mg SC N=194 | Mepolizumab 75 mg IV N=191 | Placebo N=191 | |
|---|---|---|---|
| Mean age in years (range) | 51 (12 - 81) | 50 (13 - 82) | 49 (12 - 76) |
Gender, n (%) Male Female | 78 (40) 116 (60) | 85 (45) 106 (55) | 84 (44) 107 (56) |
| Mean duration of asthma in years (SD) | 20.5 (12.9) | 19.8 (14.0) | 19.5 (14.6) |
| Mean % Predicted pre-bronchodilator FEV1 (SD) | 59.3 (17.6) | 61.4 (18.3) | 62.4 (18.1) |
| Geometric mean baseline blood eosinophil count (SD on log scale) - GI/L | 0.29 (1.050) | 0.28 (0.987) | 0.32 (0.938) |
| Mean number of exacerbations in the previous year (SD) | 3.8 (2.7) | 3.5 (2.2) | 3.6 (2.8) |
Study Results
The reduction in the rate of clinically significant exacerbations of asthma was statistically significant (p<0.001) for both mepolizumab treatment groups compared with placebo (Table 11).
Compared with placebo, the reduction in the rate of exacerbations that required hospitalization or emergency room visits was statistically significant for NUCALA 100 mg SC, but not for mepolizumab 75 mg IV (Table 11). Additionally, the rate of clinically significant exacerbations requiring hospitalization per year in the NUCALA 100 mg SC, mepolizumab 75 mg IV, and placebo treatment groups were 0.03, 0.06 and 0.10, respectively.
Table 11 Summary of Primary and Secondary Endpoints at Week 321
NUCALA 100 mg SC N= 194 | Mepolizumab 75 mg IV N = 191 | Placebo N= 191 | |||||||
|---|---|---|---|---|---|---|---|---|---|
| Frequency of Clinically Significant Exacerbations (Primary Endpoint) | |||||||||
| Exacerbation rate per year | 0.83 | 0.93 | 1.74 | ||||||
Percent reduction vs. placebo Rate ratio (95% CI) p-value2 | 53% 0.47 (0.35, 0.64) <0.001 | 47% 0.53 (0.40, 0.72) <0.001 | - | ||||||
| Frequency of Clinically Significant Exacerbations Requiring Hospitalizations/Emergency Room Visits (Secondary Endpoint) | |||||||||
| Exacerbation rate per year | 0.08 | 0.14 | 0.20 | ||||||
Percent reduction vs. placebo Rate ratio (95% CI) p-value2 | 61% 0.39 (0.18, 0.83) 0.015 | 32% 0.68 (0.33, 1.41) 0.299 | - | ||||||
1Analysis was performed using a negative binomial model, which included covariates for treatment, use of maintenance oral corticosteroids, geographic region, number of exacerbations in the previous year, and baseline percentage of the predicted FEV1.
2 Type 1 error rate was controlled using a closed-testing procedure.
At Week 32, the mean change from baseline in pre-bronchodilator FEV1 in the NUCALA 100 mg SC, mepolizumab 75 mg IV, and placebo treatment groups were 183 mL, 186 mL and 86 mL, respectively.
Health-related quality of life was measured using St. Georges Respiratory Questionnaire (SGRQ). At Week 32, mean changes from baseline in SGRQ scores in the NUCALA 100 mg SC, mepolizumab 75 mg IV, and placebo treatment groups were -16.0, -15.4 and -9.0, respectively.
SteroId ReductIon with mepolizUmab Study (SIRIUS) Study
Study Design
SIRIUS was a 24-week, randomized, placebo-controlled, double-blind, parallel group study that evaluated the effect of NUCALA 100 mg administered subcutaneously (SC) on reducing the requirement for maintenance oral corticosteroids (OCS) while maintaining asthma control in patients with severe eosinophilic asthma. A total 135 subjects were enrolled in the study (Table 12).
Subjects were required to have blood eosinophils of ≥150 cells/mcL at initiation (within 6 weeks of dosing) or blood eosinophils of ≥300 cells/mcL within 12 months of enrollment. Similar to MENSA, subjects had a documented requirement for high-dose ICS (or medium-dose ICS for adolescents) with an additional controller(s) in the previous year. Additionally, all subjects were required to be on regular maintenance treatment with OCS (5 to 35 mg/day prednisone or equivalent). No exacerbation history was required; however the majority of patients (84%) had a history of at least one exacerbation in the previous year.
The study included a run-in optimization phase of 3-8 weeks, in which subjects’ OCS dose was adjusted weekly, according to a pre-defined schedule, to establish the lowest dose of OCS required to maintain asthma control (hereafter referred to as baseline dose). Subjects were then randomized to receive either adjunctive NUCALA 100 mg SC or placebo treatment once every 4 weeks for 24 weeks. Reduction of the OCS dose occurred every 4 weeks (between Week 4 and Week 20) according to predefined schedule, and taking into account asthma control and adrenal insufficiency. The OCS dose was reduced until zero, or to the lowest possible dose required to maintain control during the 20 week OCS reduction phase. No further adjustment was made to the OCS dose following Week 20.
The primary endpoint was the percent reduction of OCS dose over Weeks 20 to 24 compared with the dose of OCS established during the run-in optimization phase at the start of the study. Predefined categories included percent reductions ranging from 90-100% reduction, to no decrease in the OCS dose from the end of the optimisation phase.
During the study, the percentage of patients who discontinued treatment and withdrew prematurely from the NUCALA 100 mg SC group and placebo group was 4% and 6%, respectively. The most common reason for discontinuation of treatment was due to adverse events (5% placebo, 4% NUCALA 100 mg SC).
Patient Demographics and Baseline Characteristics
Demographics and baseline characteristics were balanced between treatment groups (Table 12). With the exception of OCS, subjects continued their baseline asthma therapy throughout the trial i.e. high-dose ICS (or medium-dose ICS for adolescents) with an additional controller(s).
Table 12 Summary of Patient Demographics and Baseline Characteristics
NUCALA 100 mg SC N=69 | Placebo N=66 | |
|---|---|---|
| Mean age in years (range) | 50 (16 - 74) | 50 (28 - 70) |
Gender, n (%) Male Female | 25 (36) 44 (64) | 36 (55) 30 (45) |
| Mean duration of asthma in years (SD) | 17.4 (11.8) | 20.1 (14.4) |
| Mean % Predicted pre-bronchodilator FEV1 (SD) | 59.6 (17.0) | 57.8 (18.5) |
| Geometric mean baseline blood eosinophil count (SD on log scale) - GI/L | 0.25 (1.245) | 0.23 (1.001) |
| Mean number of exacerbations in the previous year (SD) | 3.3 (3.4) | 2.9 (2.8) |
| Mean baseline daily OCS dose (mg) | 12.4 | 13.2 |
Study Results
Subjects receiving NUCALA 100 mg SC achieved greater reductions in OCS dose compared to subjects receiving placebo, while maintaining asthma control (Table 13).
Table 13 Percent Reduction in OCS from Baseline at Weeks 20-24
NUCALA 100 mg SC N= 69 | Placebo N= 66 | ||
|---|---|---|---|
| Percent Reduction in OCS from Baseline at Weeks 20-24 (%) | |||
90% - 100% 75% - <90% 50% - <75% >0% - <50% No decrease in OCS/lack of asthma control/withdrawal from treatment | 16 (23%) 12 (17%) 9 (13%) 7 (10%) 25 (36%) | 7(11%) 5 (8%) 10 (15%) 7(11%) 37 (56%) | |
For Weeks 20-24, 37 (54%) subjects in the NUCALA 100 mg SC group versus 22 (33%) subjects in the placebo group achieved ≥50% reduction in the daily OCS dose; 37 (54%) subjects in the NUCALA 100 mg SC group versus 21 (32%) subjects in the placebo group achieved a reduction in the daily OCS dose to ≤5.0 mg; and 10 (14%) subjects in the NUCALA 100 mg SC group achieved a total (100%) reduction in OCS dose to 0 mg compared with 5 (8%) subjects in the placebo group.
Pediatrics
In the double-blind placebo-controlled study MENSA (Table 9), there were 25 adolescents (12 to 17 years of age); 9 received mepolizumab 75 mg IV, 7 received NUCALA 100 mg SC, and 9 received placebo. Adolescents had a reduction in the rate of clinically significant exacerbation that trended in favour of mepolizumab.
Study 200363 was a multi-centre, open-label, uncontrolled, study that enrolled 36 children (6 to 11 years of age) with severe eosinophilic asthma. Subjects received 40 mg SC of NUCALA (for a weight < 40 kg) or 100 mg SC of NUCALA (for a weight ≥ 40 kg). The short-term phase (12 weeks) characterized the pharmacokinetics and pharmacodynamics of mepolizumab in children (see 10.3 Pharmacokinetics and 10.2 Pharmacodynamics). Following a treatment interruption of 8 weeks, the long-term phase (52 weeks) assessed safety and tolerability.
The efficacy of NUCALA in children (6 to 11 years of age) for a 40 mg SC dose is extrapolated from efficacy in adults and adolescents with support from population pharmacokinetic analyses and pharmacodynamic analyses. The disease course, pathophysiology, and drug effects in children are assumed to be sufficiently consistent to adults and adolescents at the same exposure levels.
Chronic Rhinosinusitis with Nasal Polyps
Study Design
The efficacy and safety of NUCALA 100 mg SC as an adjunct to maintenance treatment of patients with CRSwNP was evaluated in a phase III, multi-centre, randomised, double-blind, placebo-controlled study of 52 weeks duration in 407 patients aged 18 years and older. Subjects received NUCALA 100 mg SC or placebo once every 4 weeks while continuing intranasal corticosteroid therapy (see Table 14). Patients must have received background intranasal corticosteroid for ≥8 weeks pre screening. Patients had recurrent CRSwNP, having had at least 1 surgery for the removal of nasal polyps within the previous 10 years. Patients were required to have nasal polyps symptoms with a nasal obstruction visual analog scale (VAS) score of >5 out of a maximum score of 10, an overall symptoms VAS score >7 out of a maximum score of 10, and an endoscopic bilateral nasal polyp score (NPS) of ≥5 out of a maximum score of 8 (with a minimum score of 2 in each nasal cavity).
The co-primary endpoints were change from baseline to week 52 in total endoscopic NPS (0 to 8 scale) as graded by independent blinded assessors and change from baseline in nasal obstruction VAS score (0 to 10 scale) during weeks 49 to 52. For NPS, polyps on each side of the nose were graded on a categorical scale (0 = no polyps, 1 = small polyps in the middle meatus not reaching below the inferior border of the middle concha, 2 = polyps reaching below the lower border of the middle turbinate, 3 = large polyps reaching the lower border of the inferior turbinate or polyps medial to the middle concha, 4 = large polyps causing almost complete congestion/obstruction of the inferior meatus). The total score was the sum of the right and left scores. Nasal obstruction VAS score was reported daily by the patients (0 to 10 scale [0 = none, 10 = as bad as you can imagine]).
Table 14 Summary of Trial Design for 205687
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| 205687 | 52-week, multi-centre, randomised, double-blind, placebo-controlled study of NUCALA 100 mg SC in subjects with CRSwNP with concomitant background intranasal corticosteroid therapy. | NUCALA 100 mg SC Placebo Duration: 52 weeks | n=206 n=201 Total: 407 | 49 (18-82) | Female: 143 (35%) Male: 264 (65%) |
SC = subcutaneous; CRSwNP = chronic rhinosinusitis with nasal polyps.
Patient Demographics and Baseline Characteristics
The baseline characteristics of subjects in this trial are provided in Table 15. See Study Results section for baseline and Week 52 values for efficacy endpoints including endoscopic NPS, symptom visual analog scale [VAS] scores, and SNOT-22.
Table 15 Summary of baseline characteristics
NUCALA 100 mg SC N=206 | Placebo N=201 | |
|---|---|---|
| Duration (y) of CRSwNP, mean (SD) | 11.36 (8.522) | 11.46 (8.273) |
| History of >3 surgeries for nasal polyps in previous 10 years, n (%) | 51 (24) | 73 (35) |
| OCS use (>1 course) in previous 12 months, n (%) | 106 (51) | 91 (45) |
| Geometric mean eosinophil count at baseline, cells/mcL (95% CI) | 390 | 410 |
| Asthma, n (%) | 140 (68) | 149 (74) |
| AERD, n (%) | 45 (22) | 63 (31) |
CRSwNP = chronic rhinosinusitis with nasal polyps, SD = standard deviation, OCS = oral corticosteroid, AERD = aspirin-exacerbated respiratory disease.
Study Results
Results of Study 205687 in patients with CRSwNP
The results for the co-primary and key secondary endpoints in CRSwNP are presented in Table 16.
Table 16 Analyses of co-primary and key secondary endpoints (Intent To Treat populationa)
Mepolizumab 100 mg SC (N=206) | Placebo (N=201) | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| Co-primary endpoint: Total Endoscopic Score at week 52 b | |||||||||
| Median score at baseline (min, max) | 5.0 (2, 8) | 6.0 (0, 8) | |||||||
| Median change from baseline | -1.0 | 0.0 | |||||||
| Adjusted treatment difference in medians (95% CI)c | -0.73 (-1.11, -0.34)d | ||||||||
| Co-primary endpoint: Nasal obstruction VAS score (weeks 49 to 52)b | |||||||||
| Median score at baseline (min, max) | 9.01 (6.54, 10.00) | 9.14 (5.31, 10.00) | |||||||
| Median change from baseline | -4.41 | -0.82 | |||||||
| Adjusted treatment difference in medians (95% CI)c | -3.14 (-4.09, -2.18)d | ||||||||
| Key secondary endpoint: NP surgery at week 52e,f | |||||||||
| Patients having surgery by Week 52 | 18 (9%) | 46 (23%) | |||||||
| Hazard ratio (95% CI)g | 0.43 (0.25, 0.76) | ||||||||
VAS = visual analogue scale
a Intent to treat population: Randomised subjects who received at least one dose of study treatment b Subjects with nasal surgery/sinuplasty prior to visit assigned their worst observed score prior to nasal surgery/sinuplasty. Those who withdrew from study with no nasal surgery/sinuplasty assigned their worst observed score prior to study withdrawal.
c Quantile regression model with covariates of treatment group, geographic region, baseline score and log(e) baseline blood eosinophil count.
d p <0.001 based on Wilcoxon rank-sum test.
e NP surgery was defined as any procedure involving instruments resulting in incision and removal of tissue [polypectomy] in the nasal cavity.
f A pre-defined hierarchical testing procedure was used to control overall Type I error for secondary endpoints; see Table 17 for additional secondary endpoints included in the testing procedure.
g Cox Proportional Hazards model with covariates of treatment group, geographic region, baseline total endoscopic score, baseline nasal obstruction VAS score, log(e) baseline blood eosinophil count and number of previous surgeries (1, 2, >2 as ordinal). p=0.003.
The key secondary endpoint was the time to first NP surgery up to Week 52 (see Figure 2).
Figure 2 Kaplan Meier Curve for Time to First Nasal Polyps surgery
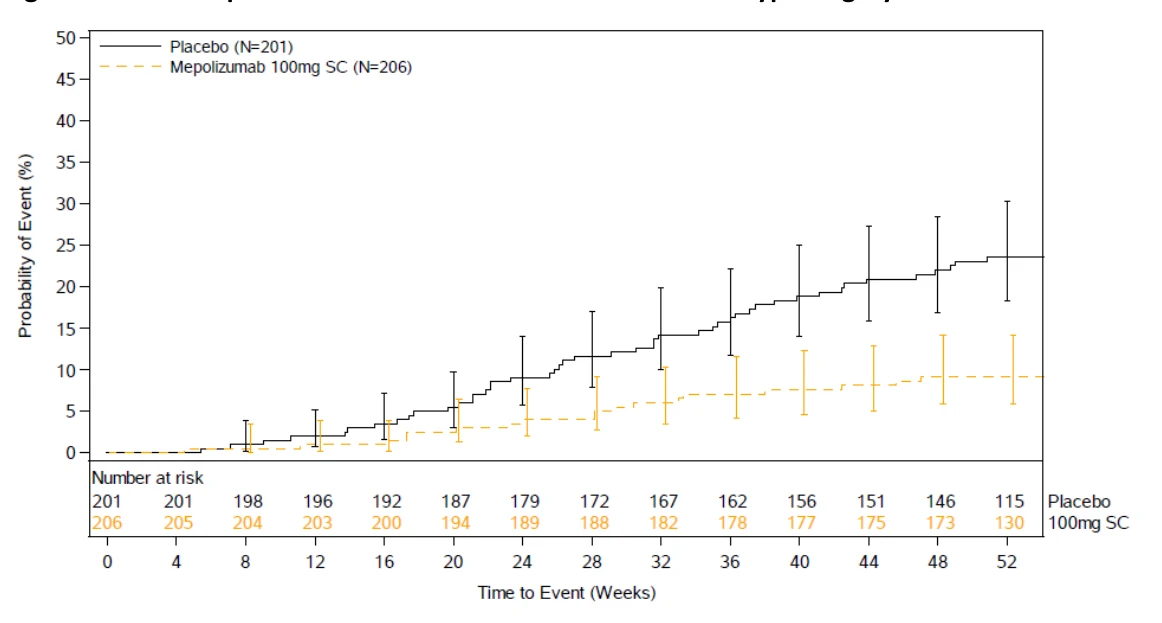
Results of Secondary Endpoints
Data from the other secondary endpoints are presented in Table 17.
All VAS scores were collected daily by the patients and reported on a 0 to 10 scale (0 = none, 10 = as bad as you can imagine). SNOT-22 is a disease-specific measure of health-related quality of life that includes 22 items assessing symptoms and symptom impact associated with CRSwNP, with each item scored from 0 (no problem) to 5 (problem as bad as it can be) and with a total score ranging from 0 to 110.
Table 17 Results of secondary endpoints in the Intent To Treat populationa
NUCALA 100 mg SC (N=206) | Placebo (N=201) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Overall VAS Score (Weeks 49-52) b | ||||||||||
| Median score at baseline (min, max) | 9.12 (7.17, 10.00) | 9.20 (7.21, 10.00) | ||||||||
| Median change from baseline | -4.48 | -0.90 | ||||||||
| Adjusted treatment difference in medians (95% CI)c | -3.18 (-4.10, -2.26) d | |||||||||
| SNOT-22 Total Score at Week 52 b | ||||||||||
| n | 205 | 198 | ||||||||
| Median score at baseline (min, max) | 64.0 (17, 105) | 64.0 (19, 110) | ||||||||
| Median change from baseline | -30.0 | -14.0 | ||||||||
| Adjusted treatment difference in medians (95% CI)c | -16.49 (-23.57, -9.42) d | |||||||||
| Patients Requiring Systemic Steroids for Nasal Polyps up to Week 52 | ||||||||||
| Number of patients with ≥1 course | 52 (25) | 74 (37) | ||||||||
| Odds Ratio to Placebo (95% CI)e | 0.58 (0.36, 0.92) | |||||||||
| Composite VAS Score - Nasal Symptoms (Weeks 49-52) b,f | ||||||||||
| Median score at baseline (min, max) | 9.11 (4.91, 10.00) | 9.18 (6.03, 10.00) | ||||||||
| Median change from baseline | -3.96 | -0.89 | ||||||||
| Adjusted treatment difference in medians (95% CI)c | -2.68 (-3.44, -1.91) d | |||||||||
| Loss of Smell VAS Score (Weeks 49-52)b | ||||||||||
| Median score at baseline (min, max) | 9.97 (0.94, 10.00) | 9.97 (6.69, 10.00) | ||||||||
| Median change from baseline | -0.53 | 0.00 | ||||||||
| Adjusted treatment difference in medians (95% CI)c | -0.37 (-0.65, -0.08) d | |||||||||
VAS = visual analogue scale, SNOT-22 = Sino-Nasal Outcome Test
a Intent to treat population: Randomised subjects who received at least one dose of study treatment. Multiplicity controlled through testing of secondary endpoints following a pre-defined hierarchical testing procedure.
b Patients with nasal surgery/sinuplasty prior to visit assigned their worst observed score prior to nasal surgery/sinuplasty. Those who withdrew from study with no nasal surgery/sinuplasty assigned their worst observed score prior to study withdrawal.
c Quantile regression model with covariates of treatment group, geographic region, baseline score and log(e) baseline blood eosinophil count.
d p<0.001 based on Wilcoxon rank-sum test.
e Logistic regression model with covariates of treatment group, geographic region, number of OCS courses for NP in last 12 months (0, 1, >1 as ordinal), baseline total endoscopic score, baseline nasal obstruction VAS score and log(e) baseline blood eosinophil count. p=0.020.
f Composite VAS score comprised of individual VAS scores of nasal obstruction, nasal discharge, mucus in the throat and loss of smell.
Endpoints in patients with Asthma
In 289 (71%) patients with co-morbid asthma, pre-specified analyses showed improvements consistent with those seen in the ITT population in the co-primary endpoints of change from baseline in total endoscopic NP score at Week 52 and change from baseline nasal obstruction VAS Score during Weeks 49-52.
Improvements (decreases) were seen in Asthma Control Questionnaire (ACQ-5) and asthma exacerbations from post-hoc analyses. For ACQ-5 at Week 52 the mean (SE) changes from baseline were -1.12 (0.095) and -0.46 (0.093) in the mepolizumab and placebo treatment groups respectively
Six (4%) patients who received mepolizumab had 6 asthma exacerbations and 11 (7%) patients in the placebo group had 20 exacerbations up to Week 52.
Chronic Obstructive Pulmonary Disease
The efficacy and safety of NUCALA (Mepolizumab) as an add-on maintenance treatment in adult subjects with Chronic Obstructive Pulmonary Disease (COPD) characterized by raised blood eosinophils was evaluated in three phase III clinical trials of 52 to 104 weeks duration (Table 18).
Table 18 Summary of Trial Designs in Chronic Obstructive Pulmonary Disease
| Study # | Trial design | Dosage, route of administration and duration | Study subjects | Mean age (Min-Max) | Sex |
|---|---|---|---|---|---|
| 208657 (MATINEE) | Multi-centre, randomized, placebo-controlled, double-blind, parallel-group, phase III study to evaluate the efficacy and safety of mepolizumab in subjects with COPD experiencing frequent exacerbations and characterized by eosinophil levels | NUCALA 100 mg SC Placebo Duration: 52-104 weeks | N=403a N=401a Total: 804 | 66 years (39-91) | Female: 253 (31%) Male: 551 (69%) |
MEA117106 (METREX) | Multi-centre, randomized, placebo-controlled, double-blind, parallel-group phase III study to evaluate the efficacy and safety of mepolizumab in subjects with COPD at risk of exacerbation | NUCALA 100 mg SC Placebo Duration: 52 weeks | N=233b N=184c N=229b N=190c Total: 836 | 65 years (39-85) | Female: 316 (38%) Male: 520 (62%) |
| MEA117113 (METREO) | Multi-centre, randomized, placebo-controlled, double-blind, parallel-group, phase III study to evaluate the efficacy and safety of two doses of mepolizumab in subjects with COPD at risk of exacerbation | NUCALA 100 mg SC Mepolizumab 300 mg SC Placebo Duration: 52 weeks | N=223 b N=225 b N=226 b Total: 674 | 65 years (42-88) | Female: 228 (34%) Male: 446 (66%) |
SC = subcutaneous, COPD = Chronic Obstructive Pulmonary Disease
a Subjects with blood eosinophil levels of ≥ 300 cells/mcL at screening and ≥150 cells/mcL within the previous 12 months
b Subjects with blood eosinophil levels of ≥150 cells/mcL at screening or ≥300 cells/mcL within the previous 12 months
c Stratum of subjects with blood eosinophil levels of <150 cells/mcL at screening and no evidence of blood eosinophil levels ≥300 cells/mcL within the previous 12 months
Study 208657 (MATINEE)
Study Design
The efficacy of NUCALA (100 mg SC every 4 weeks) added to SoC was evaluated in a multi-centre, randomized, placebo-controlled, double-blind, phase III pivotal trial (208657, MATINEE) in adult subjects with COPD with an eosinophilic phenotype. Subjects were required to have a blood eosinophil count of ≥300 cells/mcL at screening and ≥150 cells/mcL in the 12 months prior. Enrolled subjects had moderate to very severe airflow limitation (post-bronchial FEV1 of 20-80% predicted) and a history of moderate to severe exacerbations (at least 1 severe exacerbation requiring hospitalization, or 2 moderate exacerbations requiring treatment with systemic corticosteroids with or without antibiotics) despite receiving maintenance inhaled triple therapy (inhaled corticosteroid (ICS), long-acting beta agonist (LABA), and long-acting muscarinic antagonist (LAMA)) for at least 3 months prior to screening with continued treatment for the duration of the trial. To maximize the opportunity for collection of exacerbation data, the treatment duration was extended to beyond 52 weeks and up to 104 weeks.
The modified intent-to-treat population (mITT) consisted of a total of 804 adult subjects randomized 1:1 to receive subcutaneous injection of either NUCALA 100 mg in addition to SoC (N = 403) every 4 weeks until Week 52 to Week 104 (for a total of 13 to 26 doses) or matched placebo (N = 401).
Patient Demographics and Baseline Characteristics
The demographics and baseline characteristics of the patients are provided in Table 19.
Table 19 Summary of baseline characteristicsa
NUCALA 100 mg SC N=403 | Placebo N=401 | |
|---|---|---|
| Age (y) of patients, mean (SD) | 66.4 (8.10) | 66.0 (7.91) |
| Female, n (%) | 127 (32) | 126 (31) |
| White, n (%) | 338 (84) | 335 (84) |
| Current smokers, n (%) | 111 (28) | 111 (28) |
| Average smoking history (pack-years), mean (SD) | 43.2 (25.99) | 42.7 (23.74) |
| Duration of COPD (y), mean (SD) | 10.2 (6.65) | 9.7 (5.88) |
| mMRC score ≥ 2 (range 0-4), n (%) | 310 (77) | 301 (75) |
| Emphysema onlyb, n (%) | 120 (30) | 132 (33) |
| Chronic bronchitis onlyb, n (%) | 170 (42) | 168 (42) |
| Emphysema and chronic bronchitisb, n (%) | 81 (20) | 62 (15) |
| Mild airflow limitation: ≥80% predicted FEV1, n (%) | 2 (<1) | 3 (<1) |
| Moderate airflow limitation: ≥50%-<80% predicted FEV1, n (%) | 168 (42) | 181 (45) |
| Severe airflow limitation: ≥30%-<50% predicted FEV1, n (%) | 180 (45) | 160 (40) |
| Very severe airflow limitation: <30% predicted FEV1, n (%) | 53 (13) | 57 (14) |
| Post-bronchodilator % predicted FEV1, mean (SD)c | 48.1 (15.73) | 48.2 (15.83) |
| Post-bronchodilator FEV1/FVC ratio, mean (SD) c | 0.49 (0.121) | 0.49 (0.127) |
| Number of moderate or severe exacerbations in previous year, mean (SD) | 2.3 (0.98) | 2.2 (0.90) |
| One or more severe exacerbation in previous year, n (%) | 88 (22) | 77 (19) |
| CAT score, mean (SD) | 19.2 (6.95) | 19.1 (6.75) |
| SGRQ score, mean (SD) | 55.3 (17.73) | 53.9 (17.86) |
| E-RS: COPD score, mean (SD) | 13.16 (6.796) | 12.94 (6.790) |
| Geometric mean eosinophil count at screening, cells/mcL (95% CI) | 480 (460, 500) | 480 (460, 500) |
mMRC = modified Medical Research Council, FEV1 = forced expiry volume in 1 second, FVC = forced vital capacity, CAT = COPD Assessment Test, SGRQ = St. George’s Respiratory Questionnaire, E-RS: COPD = Evaluating Respiratory Symptoms in COPD
amITT (modified Intent-to-Treat) population
b COPD subtype based on Investigator assessment. 544 (68%) patients reported symptoms of chronic bronchitis based on SGRQ.
cAs measured at screening.
The primary efficacy endpoint of the trial was the annualized rate of moderate (defined as worsening of COPD symptoms requiring treatment with oral/systemic corticosteroids and/or antibiotics) or severe exacerbations (defined as requiring hospitalization or resulting in death) over the 52-104 week treatment period. The key secondary endpoints included: i) the time to first moderate/severe exacerbation over the 52-104 week treatment period; ii) three symptoms and health-related quality of life endpoints: COPD Assessment Test (CAT) responders at week 52 (defined as a reduction in score of 2 or more from baseline); St. George’s Respiratory Questionnaire (SGRQ) responders at week 52 (defined as a reduction in score of 4 or more from baseline); and Evaluating Respiratory Symptoms in Chronic Obstructive Pulmonary Disease (E-RS: COPD) responders at week 52 (defined as a reduction in score of
2 or more from baseline) and iii) the annualized rate of exacerbations requiring Emergency Department (ED) visit and/or hospitalization.
Study Results
Exacerbations
The key efficacy results regarding the exacerbation endpoints with NUCALA in subjects with COPD are presented in Table 20 for the mITT population of the MATINEE study.
Table 20 COPD Exacerbation Endpoints over 52-week to 104-week of treatment in the Modified Intent-To-Treat (mITT) Population of the MATINEE study
NUCALA 100 mg SC (N=403) | Placebo (N=401) | ||||
|---|---|---|---|---|---|
| Annualized Rate of moderatea or severeb exacerbationsc | |||||
| Exacerbation rate per year | 0.80 | 1.01 | |||
Percent rate reduction Rate ratio vs. placebo (95% CI) | 21% 0.79* (0.66, 0.94) | ||||
| Time to first moderate or severe exacerbation | |||||
| Median time to first exacerbationd (days) | 419 | 321 | |||
Percent risk reduction Hazard ratio vs. placebo (95% CI) | 23% 0.77* (0.64, 0.93) | ||||
COPD = Chronic Obstructive Pulmonary Disease, SC = subcutaneous, CI = Confidence Interval
a Exacerbations treated with oral/systemic corticosteroids and/or antibiotics.
b Exacerbations requiring hospitalization or resulting in death.
c Results obtained from a negative binomial model with an offset term to adjust for different follow-up durations and fixed effects of smoking status, number of exacerbations in previous year, baseline disease severity and geographic region.
d Kaplan Meier estimate
* Statistically significant versus placebo based on the pre-defined testing hierarchy at the overall 2-sided 0.05 significance level.
NUCALA numerically reduced the annualized rate of COPD exacerbations requiring emergency department visits and/or hospitalization when compared with placebo but did not meet statistical significance (rate ratio [RR] of 0.65; 95% CI: 0.43, 0.96).
Symptoms and health-related quality of life assessments
The results of symptoms and health-related quality of life endpoints (CAT, SGRQ and E-RS: COPD) were not statistically significant. The SGRQ responder rate (defined as a reduction in score of 4 or more from baseline) at Week 52 was 50% for NUCALA 100 mg compared with 46% for placebo.
Study MEA117113 (METREO) and Study MEA117106 (METREX)
Prior to MATINEE, the efficacy of NUCALA 100 mg in adult subjects with COPD was evaluated in two additional 52-week multi-centre, randomized, placebo-controlled, double-blind, parallel-group, phase III trials, study MEA117113 (METREO) and study MEA117106 (METREX) (Table 18). METREO enrolled subjects with a screening blood eosinophil count ≥ 150 cells/mcL or ≥ 300 cells/mcL within the previous 12 months. METREX enrolled subjects regardless of blood eosinophil count, and stratified subjects into high (defined as ≥ 150 cells/mcL at screening or ≥ 300 cells/mcL within the previous 12 months) and low strata (defined as <150 cells/mcL at screening and no evidence of a blood eosinophil count ≥ 300 cells/mcL within the previous 12 months). Subjects enrolled had a history of exacerbations (at least 1 severe, or 2 moderate) in the previous 12 months despite regular use of ICS plus 2 additional COPD maintenance therapies (LAMA, LABA, phosphodiesterase-4 inhibitor or methylxanthine).
A total of 1285 subjects with COPD were randomized to receive either NUCALA 100 mg (N = 223 and N = 417 subjects in METREO and METREX respectively) every 4 weeks until Week 52, or matched placebo (N = 226 and N = 419 subjects in METREO and METREX respectively).
The primary efficacy endpoint in METREO and METREX was the annualized rate of moderate (defined as worsening of COPD symptoms requiring treatment with systemic corticosteroids or antibiotics) or severe (defined as requiring hospitalization or resulting in death) exacerbations.
In the primary endpoint, no statistically significant difference with NUCALA 100 mg compared to placebo was observed in METREO (rate ratio [RR] of 0.80 (95% CI: 0.65, 0.98) after multiplicity adjustment). A significant difference was only observed in subjects in the high stratum of METREX (RR of 0.82 (95% CI: 0.68, 0.98)). Most secondary endpoints in METREO and METREX were not statistically significant.
METREO and METREX took place prior to MATINEE, with data from these two studies informing the refined inclusion criteria for blood eosinophil levels in the confirmatory study MATINEE. COPD patients with a history of resolved asthma were permitted in METREO and METREX, but not in MATINEE.
Eosinophilic Granulomatosis with Polyangiitis
Study Design
The efficacy and safety of mepolizumab as an adjunct to oral corticosteroids for the treatment of patients with EGPA was evaluated in a phase III, multi-centre, randomized, double-blind, placebo-controlled study of 52 weeks duration in 136 subjects aged 18 years and older. Subjects received 300 mg of NUCALA or placebo administered subcutaneously once every 4 weeks, while maintaining stable oral corticosteroid therapy (Table 21). Starting at Week 4, oral corticosteroid dose could be tapered during the treatment period at the discretion of the investigator. The co-primary endpoints were: 1) the total accrued duration of remission over the 52-week treatment period, defined as Birmingham Vasculitis Activity Score (BVAS) = 0 (no active vasculitis) plus oral corticosteroid dose ≤4 mg/day (prednisolone/prednisone); and 2) the proportion of subjects in remission at both Week 36 and Week 48 of treatment. Relapse of disease was defined as worsening or persistence of active disease since the last visit warranting: i) an increased dose of OCS therapy (>4 mg/day); OR ii) an increased dose or addition of immunosuppressive therapy; OR iii) hospitalization related to EGPA worsening. Worsening of active disease was characterized by: i) active vasculitis (BVAS >0); OR ii) active asthma symptoms and/or signs with a corresponding worsening in ACQ-6 score; OR iii) active nasal and/or sinus disease with a corresponding worsening in at least one of the sino-nasal symptom questions.
Table 21 Summary of Trial Design for MEA115921
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| MEA115921 | 52-week, multi-centre, randomised, double-blind, placebo-controlled study of mepolizumab in subjects with a history of relapsing or refractory EGPA on stable oral corticosteroid therapy with or without concomitant stable immunosuppressant therapya. | NUCALA 300 mg SC Placebo Duration: 52 weeks | n=68 n=68 Total: 136 | 48.5 (20-71) | Female: 80 (59%) Male: 56 (41%) |
SC = subcutaneous; EGPA = Eosinophilic Granulomatosis with Polyangiitis.
a Excluding cyclophosphamide.
Patient Demographics and Baseline Characteristics
The demographics and baseline characteristics of subjects in this trial are provided in Table 22.
Table 22 Summary of Patient Demographics and Baseline Characteristics
NUCALA 300 mg SC N=68 | Placebo N=68 | |
|---|---|---|
NUCALA 300 mg SC N=68 | Placebo N=68 | |
| Mean age (y) | 48.7 | 48.2 |
| Female, n (%) | 42 (62) | 38 (56) |
| White, n (%) | 64 (94) | 61 (90) |
| Duration (y) of EGPA, mean (SD) | 5.24 (4.398) | 5.85 (4.855) |
| History of >1 confirmed relapse in past 2 years, n (%) | 51 (75) | 49 (72) |
History/presence of Asthma plus Eosinophilia (>1.0x10⁹/L), n (%) Sino-nasal abnormality Pulmonary infiltrates, non-fixed Biopsy evidence1 Neuropathy, Mono or Poly2 ANCA positive (MPO or PR3) Cardiomyopathy3 Palpable purpura | 68 (100) 64 (94) 50 (74) 25 (37) 32 (47) 13 (19) 13 (19) 9 (13) | 68 (100) 64 (94) 48 (71) 31 (46) 24 (35) 13 (19) 7 (10) 8 (12) |
Alveolar hemorrhage4 Glomerulonephritis5 | 3 (4) 1 (1) | 1 (1) 0 |
| Refractory disease, n (%) | 34 (50) | 40 (59) |
| Recurrence of EGPA symptoms, n (%) | 33 (49) | 35 (51) |
| Failed induction treatment, n (%) | 1 (1) | 5 (7) |
| Baseline BVAS, median (range) | 1 (0-22) | 2 (0-19) |
| Baseline oral corticosteroida daily dose (mg), median (range) | 12 (7.5-40) | 11 (7.5-50.0) |
| Receiving immunosuppressive therapy, n (%) | 41 (60) | 31 (46) |
Baseline ACQ-6 Score Category6,7, n (%) ≤0.75 >0.75 to <1.5 ≥1.5 | 23 (34) 19 (28) 26 (38) | 19 (28) 21 (31) 28 (41) |
1 A biopsy showing histopathological evidence of eosinophilic vasculitis, or perivascular eosinophilic infiltration, or eosinophil-rich granulomatous inflammation
2 Motor deficit or nerve conduction abnormality
3 Established by echocardiography or MRI
4 Determined by bronchoalveolar lavage
5 Hematuria, red blood cell casts, proteinuria
6 ACQ-6 score ≤0.75 = well controlled asthma, >0.75 to <1.5 = some lack of asthma control, ≥1.5 = not well controlled asthma.
7 Summarized post-hoc.
a Prednisone or prednisolone equivalent.
b Excluding cyclophosphamide.
ANCA = anti-neutrophil cytoplasmic antibodies; EGPA = eosinophilic granulomatosis with polyangiitis; SD = standard deviation;
MPO = myeloperoxidase (ANCA-MPO); PR3 = proteinase 3 (ANCA-PR3).
Study Results
Remission
Subjects receiving 300 mg of NUCALA achieved a significantly greater accrued time in remission compared with placebo (odds ratio: 5.9 [95% CI: 2.7, 13.0]; p<0.001). Additionally, a significantly larger proportion of subjects receiving 300 mg of NUCALA achieved remission at both Week 36 and Week 48 compared with placebo (odds ratio: 16.7 [95% CI: 3.6, 77.7]; p<0.001) (Table 23).
Table 23 Analyses of Co-Primary Endpoints
| Number (%) of Subjects | ||||||||
|---|---|---|---|---|---|---|---|---|
NUCALA 300 mg n = 68 | Placebo n = 68 | |||||||
| Accrued duration of remission over 52 weeks | ||||||||
| 0 weeks | 32 (47) | 55 (81) | ||||||
| >0 to <12 weeks | 8 (12) | 8 (12) | ||||||
| 12 to <24 weeks | 9 (13) | 3 (4) | ||||||
| 24 to <36 weeks | 10 (15) | 0 | ||||||
| ≥36 weeks | 9 (13) | 2 (3) | ||||||
| Odds ratio (mepolizumab/placebo)a | 5.91b | |||||||
| 95% CI | 2.68, 13.03 | |||||||
| P value | <0.001 | |||||||
| Proportion of subjects in remission at Weeks 36 and 48 | ||||||||
| Subjects in remission at Weeks 36 and 48 (%) | 22 (32) | 2 (3) | ||||||
| Odds ratio (mepolizumab/placebo) a | 16.74 | |||||||
| 95% CI | 3.61, 77.56 | |||||||
| P value | <0.001 | |||||||
aAn odds ratio >1 favors mepolizumab. b Obtained using a proportional odds regression model for ordered categorical data (incremental 12-week durations). | ||||||||
Statistically significant differences in favour of mepolizumab for these endpoints were also demonstrated by the European League Against Rheumatism (EULAR) definition of remission (i.e., BVAS = 0 plus oral corticosteroid dose ≤7.5 mg/day (prednisolone/prednisone)).
A larger proportion of subjects receiving 300 mg of NUCALA (n=13; 19%) achieved remission within the first 24 weeks of treatment and remained in remission for the remainder of the 52-week treatment period compared with placebo (n=1; 1%).
Relapse
The time to first relapse was significantly longer for subjects receiving 300 mg of NUCALA compared with placebo (hazard ratio: 0.32 [95% CI: 0.21, 0.50]; p<0.001) (Figure 3). The incidence and number of each potential cause for relapse (i.e., vasculitis, asthma, sino-nasal) were lower in subjects treated with mepolizumab compared with placebo.
Figure 3 Kaplan-Meier Plot of Time to First Relapse
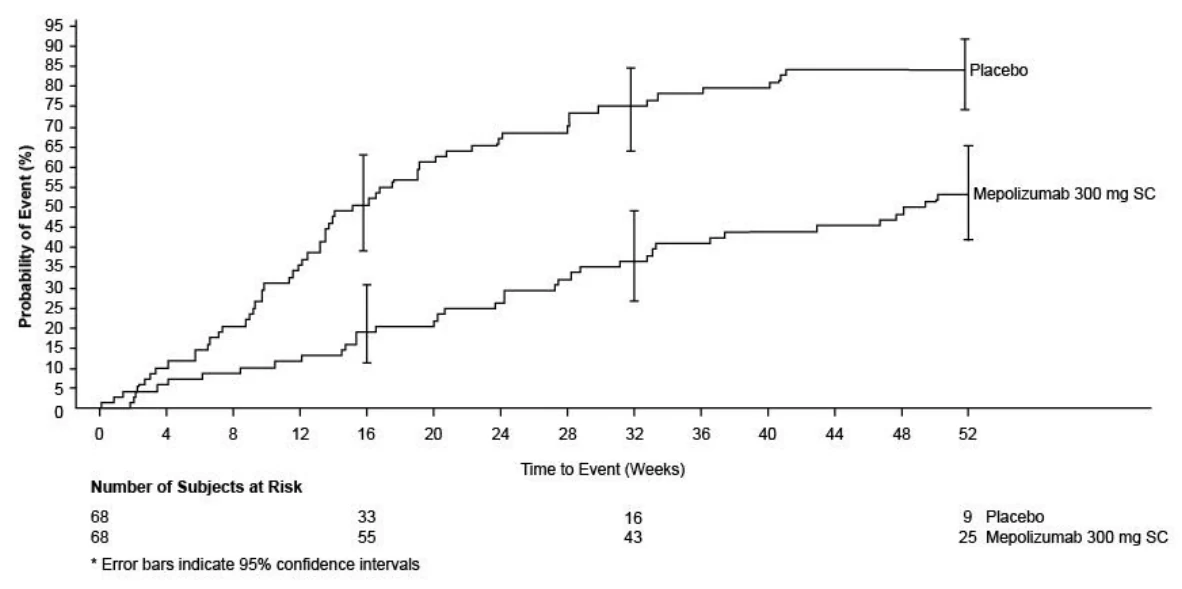
Oral Corticosteroid Reduction
Subjects receiving 300 mg of NUCALA had a significantly greater reduction in average daily oral corticosteroid dose compared with subjects receiving placebo during Weeks 48 to 52 (odds ratio: 0.20 [95% CI 0.09, 0.41]; p<0.001) (Table 24).
Table 24 Average Daily Oral Corticosteroid Dose during Weeks 48 to 52
| Average Daily Oral Corticosteroid Dose | Number (%) of Subjects | |
|---|---|---|
NUCALA 300 mg Subcutaneous n = 68 | Placebo n = 68 | |
| 0 | 12 (18) | 2 (3) |
| >0 to ≤4.0 mg | 18 (26) | 3 (4) |
| >4.0 to ≤7.5 mg | 10 (15) | 18 (26) |
| >7.5 mg | 28 (41) | 45 (66) |
| Comparison: mepolizumab/placeboa | ||
| Odds ratio | 0.20 | |
| 95% CI | 0.09, 0.41 | |
| P value | <0.001 | |
a Analyzed using a proportional odds model with covariates of treatment group, baseline oral corticosteroid daily dose, baseline BVAS, and region. An odds ratio <1 favors mepolizumab.
Hypereosinophilic Syndrome
Study Design
The efficacy and safety of mepolizumab as an adjunct to standard therapy for the treatment of patients with HES was evaluated in a phase III, multi-centre, randomized, double-blind, placebo-controlled study of 32 weeks duration in 108 subjects aged 12 years and older (Table 25). Subjects received 300 mg of NUCALA or placebo administered subcutaneously once every 4 weeks while continuing their stable HES therapy. Standard HES therapy could include OCS and immunosuppressive or cytotoxic therapy, and subjects must have been on stable HES therapy for the 4 weeks prior to randomization. Subjects with non-hematologic secondary HES (e.g., drug hypersensitivity, parasitic helminth infection, HIV infection, non-hematologic malignancy) or FIP1L1-PDGFRα kinase-positive HES were excluded from the trial. Subjects entering the study had experienced at least two HES flares within the past 12 months and had a blood eosinophil count ≥ 1000 cells/mcL during screening. Historical HES flares for the trial entry criteria were defined as HES-related worsening of clinical symptoms or blood eosinophil counts requiring an escalation in therapy.
The primary endpoint of study 200622 was the proportion of subjects who experienced a HES flare during the 32-week treatment period. A HES flare was defined as worsening of clinical signs and symptoms of HES or increasing blood eosinophils (on ≥ 2 occasions), resulting in the need to increase OCS (by at least 10 mg/day) or increase/add cytotoxic or immunosuppressive HES therapy.
Table 25 Summary of Trial Design for 200622
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| 200622 | 32-week, multi-centre, randomized, double-blind, placebo-controlled study of mepolizumab in subjects with a history of relapsing or refractory HES on stable oral corticosteroid therapy with or without cytotoxic or immunosuppressive HES therapy | NUCALA 300 mg SC Placebo Duration: 32 weeks | n=54 n=54 Total: 108 | 46.0 (12-82) | Female: 57 (53%) Male: 51 (47%) |
SC = subcutaneous; HES = Hypereosinophilic Syndrome.
Patient Demographics and Baseline Characteristics
The demographics and baseline characteristics of subjects in this trial are provided in Table 26.
Table 26 Summary of Baseline Characteristics
NUCALA 300 mg SC N=54 | Placebo N=54 | |
|---|---|---|
| Duration (y) of HES, mean (SD) | 5.45 (5.079) | 5.66 (8.035) |
| Number of HES flares in past 12 months, mean (SD) | 2.7 (1.28) | 2.7 (1.02) |
History/presence of HES plus Eosinophilia (>1.0x10⁹/L), n (%) Abdominal pain or bloating Breathing symptoms Chills or sweats Muscle or joint pain Nasal or sinus symptoms Skin symptoms | 54 (100) 16 (30) 30 (56) 10 (19) 24 (44) 22 (41) 25 (46) | 54 (100) 24 (44) 30 (56) 5 (9) 20 (37) 19 (35) 28 (52) |
| Baseline HES Therapy, n (%) | 54 (50) | 54 (50) |
| Any baseline HES therapy, n (%) | 50 (93) | 49 (91) |
| Oral corticosteroids, n (%) | 40 (74) | 38 (70) |
| Cytotoxic/immunosuppressive therapy, n (%) | 14 (26) | 9 (17) |
| Other HES therapya | 22 (41) | 19 (35) |
| Baseline oral corticosteroidb daily dose (mg), median (range) | 5.6 (0-50.0) | 5.6 (0-25.0) |
a Examples of ‘other’ HES therapy include but is not limited to beclometasone dipropionate, formoterol fumarate, omeprazole, salbutamol, tiotropium bromide, triamcinolone acetonide, cetirizine.
b Prednisone or prednisolone equivalent.
HES = hypereosinophilic syndrome; SD = standard deviation.
Study Results
The primary endpoint compared subjects who experienced a HES flare or withdrew from the study in the mepolizumab and placebo treatment groups over the 32-week treatment period. Secondary endpoints were time to first HES flare, proportion of subjects who experienced a HES flare during Week 20 through Week 32, rate of HES flares, and change from baseline in fatigue severity (Brief Fatigue Inventory [BFI]) item 3 (see Table 27).
Table 27 Results of Efficacy Endpoint/Analysis in the Intent to Treat population (Study 200622)
Mepolizumab N= 54 | Placebo N= 54 | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| Primary Efficacy Endpoint | |||||||||
| Proportion of subjects who experienced a HES flare | |||||||||
| Subjects with ≥1 HES flare or who withdrew from study (%) | 15 (28) | 30 (56) | |||||||
| Subjects with ≥1 HES flare (%) | 14 (26) | 28 (52) | |||||||
| Subjects with no HES flare who withdrew (%) | 1 (2) | 2 (4) | |||||||
| Risk difference a (95% CI) | -29% (-47%, -11%) | ||||||||
| p-value a | 0.001 | ||||||||
| Secondary Efficacy Endpoints b | |||||||||
| Time to first HES flare | |||||||||
| Median time to HES flare (days) | Median not reached | 172 | |||||||
| Hazard ratio c (95% CI) | 0.34 (0.18, 0.67) | ||||||||
| p-value c | 0.002 | ||||||||
| HES flares during week 20 and up to and including week 32 | |||||||||
| Subjects with ≥1 HES flare or who withdrew from study (%) | 9(17) | 19 (35) | |||||||
| Risk difference a (95% CI) | -18% (-34%, -2%) | ||||||||
| p-value a | 0.027 | ||||||||
| Rate of HES flares | |||||||||
| Estimated mean rate/year | 0.50 | 1.46 | |||||||
| Rate ratio d (95% CI) | 0.34 (0.19, 0.63) | ||||||||
| p-value d | <0.001 | ||||||||
| Change from baseline in fatigue severity based on Brief Fatigue Inventory (BFI) Item 3 (worst level of fatigue during past 24 hours) at week 32 e | |||||||||
| Median change in BFI item 3 | -0.66 | 0.32 | |||||||
| p-value f | 0.036 | ||||||||
a Generalised linear regression model for probability of HES flare adjusted for baseline OCS dose and region.
b Multiplicity was controlled using a hierarchical, closed testing procedure.
c Cox proportional hazards regression model adjusted for baseline OCS dose and region.
d Negative binomial regression model adjusted for baseline OCS dose and region.
e Brief Fatigue Inventory (BFI) Item 3 asks subjects to record their fatigue severity by having
them rate their worst level of fatigue during the past 24 hours (scale: 0 = no fatigue to 10 = as bad as you can imagine). Patients with missing data included with worst observed value.
f Wilcoxon Rank Sum p-value
16. Non-Clinical Toxicology
Intravenous and subcutaneous administrations to monkeys were associated with reductions in peripheral and lung eosinophil counts, with no toxicological findings. Eosinophils have been associated with immune system responses to some parasitic infections. Studies conducted in mice treated with anti-IL-5 antibodies or genetically deficient in IL-5 or eosinophils have not shown impaired ability to clear parasitic infections.
Carcinogenesis, Mutagenesis and Impairment of Fertility and Reproduction
Long-term animal studies have not been performed to evaluate the carcinogenic potential of mepolizumab. The mutagenic potential of mepolizumab was not evaluated. The role of IL-5 and eosinophils in tumor surveillance is poorly characterized. However, there is no evidence of defective tumor surveillance in IL-5–deficient or eosinophil-deficient mice.
There was no effect of anti–IL-5 antibodies on male and female mice on mating, fertility, and gonadal function or on early embryonic or embryofetal development in pregnant females. Studies in mice did not include a littering or functional F1 assessment. In cynomolgus monkeys, mepolizumab had no effect on pregnancy or on embryonic/fetal and postnatal development (including immune function) of the offspring. Examinations for internal or skeletal malformations were not performed. Data in monkeys demonstrate that mepolizumab crosses the placenta. Concentrations of mepolizumab were approximately 2.4 times higher in infants than in mothers for several months post-partum and did not affect the immune system of the infants. Mepolizumab was excreted into the milk of cynomolgus monkeys at concentrations that were less than 0.5% of those detected in plasma and there were no post-natal developmental effects in breastfed monkey offspring.