


Product Monograph - Octasa (Tillotts Pharma, 800 mg)
Recent Major Label Changes
| 2023-10 |
|---|---|
| 2023-10 |
| 2025-10 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................. 2
Table of Contents ................................................................................................................. 2
Part 1: Healthcare Professional Information.......................................................................... 5
- 1.
Indications..................................................................................................................... 5
1.1. Pediatrics .................................................................................................................... 5
1.2. Geriatrics .................................................................................................................... 5
- 2. Contraindications .......................................................................................................... 5
- 3. Serious Warnings and Precautions Box ........................................................................... 5
- 4.
Dosage and Administration ............................................................................................ 6
4.1. Dosing Considerations ............................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment .......................................................... 6
4.4. Administration ........................................................................................................... 6
4.5. Missed Dose ............................................................................................................... 7
- 5. Overdose ....................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition, and Packaging .................................................. 7
- 7.
Warnings and Precautions ............................................................................................. 7
General ................................................................................................................................... 8
Carcinogenesis and Genotoxicity ........................................................................................... 8
Cardiovascular ........................................................................................................................ 8
Gastrointestinal ...................................................................................................................... 8
Hepatic/biliary/pancreatic ..................................................................................................... 8
Immune .................................................................................................................................. 9
Monitoring and laboratory tests ............................................................................................ 9
Renal ....................................................................................................................................... 9
Reproductive health ............................................................................................................... 9
Skin ......................................................................................................................................... 9
7.1. Special Populations .................................................................................................. 10
7.1.1. Pregnant Women ............................................................................................. 10
7.1.2. Breastfeeding ................................................................................................... 10
7.1.3. Pediatrics .......................................................................................................... 10
7.1.4. Geriatrics .......................................................................................................... 10
- 8.
Adverse Reactions ....................................................................................................... 10
8.1. Adverse Reaction Overview ..................................................................................... 10
8.2. Clinical Trial Adverse Reactions ............................................................................... 10
8.3. Less Common Clinical Trial Adverse Reactions ........................................................ 12
8.5. Post-Market Adverse Reactions ............................................................................... 12
- 9.
Drug Interactions ......................................................................................................... 14
9.1. Serious Drug Interactions ........................................................................................ 14
9.2. Drug Interactions Overview ..................................................................................... 14
9.3. Drug-Behaviour Interactions .................................................................................... 14
9.4. Drug-Drug Interactions ............................................................................................ 14
9.5. Drug-Food Interactions ............................................................................................ 14
9.6. Drug-Herb Interactions ............................................................................................ 15
9.7. Drug-Laboratory Test Interactions........................................................................... 15
- 10.
Clinical Pharmacology .................................................................................................. 15
10.1. Mechanism of Action ............................................................................................... 15
10.2. Pharmacodynamics .................................................................................................. 15
10.3. Pharmacokinetics ..................................................................................................... 15
- 11. Storage, Stability, and Disposal .................................................................................... 17
Part 2: Scientific Information .............................................................................................. 18
- 13. Pharmaceutical Information ........................................................................................ 18
- 14.
Clinical Trials ............................................................................................................... 18
14.1. Clinical Trials by Indication ...................................................................................... 18
Treatment of Moderately Active Ulcerative Colitis ............................................................... 18
- 15. Microbiology ............................................................................................................... 20
- 16. Non-Clinical Toxicology ................................................................................................ 20
Patient Medication Information ......................................................................................... 22
Part 1: Healthcare Professional Information
1. Indications
Octasa (800 mg; mesalazine [also known as 5-aminosalicylic acid or mesalamine]) is indicated for:
- the treatment of moderately active ulcerative colitis
1.1. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
No data are available to Health Canada, therefore, Health Canada has not authorized an indication for geriatric use.
2. Contraindications
Octasa (800 mg tablet) is contraindicated in patients who:
- Are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
- Have a history of sensitivity to salicylates
- Have severe hepatic impairment (see 7. Warnings and Precautions)
- Have severe renal impairment (GFR < 30 mL/min/1.73 m2); see 7. Warnings and Precautions
- Patients with existing gastric or duodenal ulcer
- Have urinary tract obstruction
- Are unable to swallow the intact tablet
3. Serious Warnings and Precautions Box
- History of adverse drug reactions to sulfasalazine: Patients with a history of adverse drug reactions to sulfasalazine therapy should be kept under close medical supervision. Treatment must be stopped immediately if acute symptoms of intolerance occur such as abdominal cramps, acute abdominal pain, fever, severe headache and rash.
- Blood system: Serious blood dyscrasia has very rarely been reported. Octasa therapy should be stopped immediately if there is a suspicion or evidence of blood dyscrasia (signs of unexplained bleeding, bruising, purpura, anemia, persistent fever or sore throat), and patients should seek immediate medical advice. It is recommended that hematological investigations (differential blood count) are performed prior to initiation of Octasa and whilst on therapy, at the discretion of the treating physician. As a guideline, follow-up tests are recommended 14 days after commencement of treatment, then a further two to three tests at intervals of 4 weeks. If the findings are normal, follow-up tests should be carried out every 3 months. If additional symptoms occur, these tests should be performed immediately.
- Renal: Renal impairment, including minimal change nephropathy, acute and chronic interstitial nephritis, and renal failure has been reported in patients taking mesalazine products. Urinary status (dip sticks) should be determined prior to and during treatment, at the discretion of the treating physician. Caution should be exercised in patients with raised serum creatinine or proteinuria. The possibility of mesalazine-induced nephrotoxicity should be suspected in patients developing impairment of renal function during treatment. It is recommended that all patients have an evaluation of their renal function prior to initiation of Octasa therapy and repeatedly whilst on therapy. As a guideline, follow-up tests are recommended 14 days after commencement of treatment and then every 4 weeks for the following 12 weeks. Short monitoring intervals early after the start of Octasa therapy will discover rare acute renal reactions. In the absence of an acute renal reaction monitoring intervals can be extended to every 3 months and then annually after 5 years. If additional laboratory or clinical signs of renal impairment appear, these tests should be performed immediately. Treatment with Octasa should be stopped immediately if there is evidence of renal impairment and patients should seek immediate medical advice. Octasa (800 mg tablet) is contraindicated in patients with severe renal impairment (see 2. Contraindications).
- Pulmonary: Patients with pulmonary disease, in particular asthma, should be very carefully monitored during treatment with Octasa.
4. Dosage and Administration
4.1. Dosing Considerations
Patients with ulcerative colitis should be made aware that ulcerative colitis rarely remits completely. Abrupt discontinuation of Octasa (800 mg tablet) is not recommended, and may result in relapse. It is important for patients to comply with the dosage prescribed by their doctors; by doing so, the risk of relapse can be substantially reduced.
4.2. Recommended Dose and Dosage Adjustment
For the treatment of moderately active ulcerative colitis:
Adults
Usual daily adult dose is 6 Octasa (800 mg tablet) tablets (4.8 g), taken orally once daily or in divided doses with or without food.
Geriatrics (≥65 years)
The normal adult dose can be taken unless hepatic or renal function is severely impaired (see 2. Contraindications, and 7. Warnings and Precautions). No clinical studies have been carried out in geriatric population.
Health Canada has not authorized an indication for pediatric use.
4.4. Administration
- Swallow tablets whole, taking care not to break the outer coating. The outer coating is designed to remain intact, to protect the active ingredient until it reaches the terminal ileum, where the tablet coating dissolves and the contents of the tablet are released into the terminal ileum and colon.
Take Octasa (800 mg tablet) tablets only as prescribed. Do not change the number or frequency of
- tablets ingested without first consulting your physician.
- What appears to be intact or partially intact tablets may infrequently appear in the stool. If this occurs repeatedly, consult your physician.
4.5. Missed Dose
If a dose of this medication has been missed, it should be taken as soon as possible. However, if it is almost time for the next dose, skip the missed dose and go back to the regular dosing schedule. Do not take double the dose.
5. Overdose
There is little data on overdose (e.g. intended suicide with high oral doses of mesalazine). The available data do not indicate renal or hepatic toxicity. There is no specific antidote for mesalazine overdose, and treatment is symptomatic and supportive.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
Octasa 800 mg is supplied as a coated red/brown oblong tablet.
Each delayed-release tablet contains 800 mg mesalazine. Octasa consist of a conventional disintegrating tablet core formulation with a film coat containing a copolymer with a pH dependant dissolution behaviour as follows: the delayed-release tablets are designed to resist to drug substance release in acid media of the stomach and small intestine (tested at pH 1.0 and pH 6.4), whereas disintegration and drug substance release needs to occur at pH 7 (tested at pH 7.2) to ensure delivery of mesalazine at the target site, i.e. the terminal ileum and beyond.
Octasa 800 mg delayed-release tablets are available in PVC/aluminium blister strips, each containing ten tablets. The blister strips are packed in cartons containing either 20 (sample) or 180 tablets.
7. Warnings and Precautions
See 3. Serious Warnings and Precautions Box.
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral use | Tablet (delayed-release), 800 mg mesalazine | acetone, ferric oxide yellow, ferric oxide red, isopropyl alcohol, lactose monohydrate, macrogol 6000, magnesium stearate, methacrylic acid - methyl methacrylate copolymer (1:2), povidone K25, sodium starch glycolate (type A), talc and triethyl citrate. |
General
Patients with rare hereditary problems of galactose intolerance, Lapp lactase deficiency or glucose-galactose malabsorption should not take this medicine.
A limited number of reports of intact tablets in the stool have been received. What appear to be intact tablets may in some cases represent largely empty shells of the coated tablets. If intact tablets are observed in the stool repeatedly, the patient should consult his/her physician.
Mesalazine may produce red-brown urine discoloration after contact with sodium hypochlorite bleach (e.g. in toilets cleaned with sodium hypochlorite contained in certain bleaches).
Octasa (800 mg tablet) and other mesalazine-containing products have differences in formulation and release characteristics that may lead to differences in concentrations of mesalazine delivered to the colon. If it is deemed necessary to switch from one mesalazine-containing product to another mesalazine-containing product, the prescriber should carefully assess the overall benefit-risk analysis based on the patient’s clinical conditions and on all available information for the various mesalazine-containing products.
Carcinogenesis and Genotoxicity
Preclinical animal data are provided in 16. Non-Clinical Toxicology.
Cardiovascular
Mesalazine-induced cardiac hypersensitivity reactions (myo- and pericarditis) have rarely been reported with Octasa. In case of a suspected mesalazine-induced cardiac hypersensitivity, Octasa must not be reintroduced. Caution should be taken in patients with previous myo- or pericarditis of allergic background regardless of its origin.
Gastrointestinal
Acute exacerbation of the symptoms of colitis, characterized by cramping, abdominal pain, bloody diarrhea, and occasionally by nausea has been reported in patients in controlled clinical trials of Octasa (800 mg).
Octasa (800 mg) is contraindicated in patients with existing gastric or duodenal ulcer (see 2. Contraindications).
Hepatic/biliary/pancreatic
Caution should be exercised when using Octasa (or other compounds that contain or are converted to mesalazine or its metabolites) in patients with hepatic dysfunction.
In assessing liver complications, it should be kept in mind that these are frequently associated with ulcerative colitis.
There have been reports of hepatic failure and increased liver enzymes in patients with pre-existing liver disease when treated with mesalazine (also known as 5-ASA or mesalamine) products. Therefore, Octasa is contraindicated in patients with severe hepatic impairment (see 2. Contraindications). In patients with mild to moderate liver function impairment, caution should be exercised and Octasa should only be used if the expected benefit clearly outweighs the risks to the patients. Blood tests (liver function parameters such as ALT or AST) should be performed prior to and during treatment, at the discretion of the treating physician. As a guideline, follow-up tests are recommended 14 days after commencement of treatment, then a further two to three tests at intervals of 4 weeks. If the findings are normal, follow-up tests should be carried out every 3 months. If additional symptoms occur, these tests should be performed immediately.
Immune
Some patients who have experienced a hypersensitivity reaction to sulfasalazine may have a similar reaction to Octasa or to other compounds that contain, or are converted to, mesalazine.
Monitoring and laboratory tests
It is recommended that all patients have an evaluation of their renal function (urinary status via dip sticks); hepatic function (blood tests such as ALT or AST) as well as hematological investigations (differential blood count) prior to initiation of Octasa therapy and repeatedly whilst on therapy.
Neurologic
Idiopathic intracranial hypertension (pseudotumor cerebri) has been reported in patients receiving mesalazine. Patients should be warned for signs and symptoms of idiopathic intracranial hypertension, including severe or recurrent headache, visual disturbances or tinnitus. If idiopathic intracranial hypertension occurs, discontinuation of mesalazine should be considered.
Renal
Reports of renal impairment, including minimal change nephropathy, and acute or chronic interstitial nephritis have been associated with mesalazine products and pro-drugs of mesalazine. Octasa is contraindicated in patients with severe renal impairment (see 2. Contraindications). In patients with mild to moderate renal dysfunction, caution should be exercised and Octasa should be used only if the benefits outweigh the risks.
It is recommended that all patients have an evaluation of renal function prior to initiation of therapy and periodically while on treatment.
Cases of nephrolithiasis have been reported with the use of mesalazine including stones with a 100% mesalazine content. It is recommended to ensure adequate fluid intake during treatment.
Reproductive health
Fertility
No effects on fertility have been observed.
Skin
Serious Skin Reactions:
Use of mesalazine has been associated with the following serious and life-threatening skin reactions:
- Severe cutaneous adverse reactions (SCARs),
- Drug reaction with eosinophilia and systemic symptoms (DRESS),
- Stevens-Johnson syndrome (SJS),
- toxic epidermal necrolysis (TEN).
7.1. Special Populations
7.1.1. Pregnant Women
There are no adequate and well controlled studies of Octasa use in pregnant women. Limited published data on the class of mesalazine products show an increased rate of preterm birth, stillbirth and low birth weight. These adverse pregnancy outcomes are also associated with active inflammatory bowel disease. Mesalazine crosses the placenta. Animal reproduction studies of mesalazine found no evidence of fetal harm.
Octasa should only be used during pregnancy if the potential benefit outweighs the possible risk.
7.1.2. Breastfeeding
Literature reports indicate that, following oral or rectal administration of mesalazine-containing products to lactating women, small amounts of mesalazine (also known as 5-ASA or mesalamine) and higher concentrations of the metabolite N-acetyl-5-ASA are found in breast milk. The clinical significance of this has not been determined. Only limited experience during lactation in women is available to date.
When Octasa is used in nursing women, infants should be monitored for changes in stool consistency. If the infant develops diarrhea, breastfeeding should be discontinued. Cases of diarrhea in breastfed infants exposed to mesalazine have been reported.
7.1.3. Pediatrics
The safety and efficacy of Octasa have not been studied in pediatric populations. Octasa should not be used in children and adolescents under the age of 18 years.
7.1.4. Geriatrics
Use in elderly people should be handled with caution and Octasa should only be prescribed to elderly patients having a normal or non-severely impaired hepatic or renal function, see 2. Contraindications.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Octasa is generally well tolerated. Organ specific adverse drug reactions affecting the heart, lungs, liver, kidneys, pancreas, skin and subcutaneous tissue have been reported. Treatment must be stopped immediately if acute symptoms of intolerance occur such as abdominal cramps, acute abdominal pain, fever, severe headache and rash. Severe cutaneous adverse reactions (SCARs), including Drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), have been reported in association with mesalazine treatment (see 7. Warnings and Precautions). The most commonly reported adverse reactions were ulcerative colitis followed by hematuria and ketonuria.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Octasa 800 mg delayed-release tablets have been evaluated in 140 patients with mild to moderate active ulcerative colitis in one controlled study lasting for 10 weeks comparing safety and efficacy versus placebo. Treatment related undesirable effects in the Octasa group with the highest reporting rate were worsening of ulcerative colitis (3.6%), hematuria (2.9%) and ketonuria (2.1%).
Table 2 enumerates treatment related adverse reactions that occurred at a frequency of ≥1% in the Octasa and placebo treated groups. All adverse reactions associated with the use of Octasa 800 mg delayed-release tablets were of mild to moderate severity. Discontinuations due to adverse reactions occurred in 8.6% of patients in the Octasa group and in 21.3% of patients in the placebo group. Most of the drug related adverse reactions that led to study drug discontinuation were related to worsening of ulcerative colitis.
Table 2 – Adverse drug reactions related to Octasa 800 mg delayed-release tablets in mild to moderately active Ulcerative Colitis at a frequency of ≥1% versus placebo
| System organ class/preferred term | Octasa 800 mg n = 140 (%) | Placebo n = 141 (%) | ||
| Blood and lymphatic system disorders | ||||
| Anemia | 1.4 | 0.7 | ||
| Eosinophilia | 1.4 | 0.0 | ||
| Leukocytosis | 1.4 | 0.0 | ||
| Macrocytosis | 1.4 | 0.0 | ||
| Monocytopenia | 1.4 | 2.8 | ||
| Gastrointestinal disorders | ||||
| Worsening of ulcerative colitis | 3.6 | 8.5 | ||
| Hemorrhoids | 1.4 | 0.0 | ||
| Hepatobiliary disorders | ||||
| Hyperbilirubinemia | 1.4 | 1.4 | ||
| Nervous system disorders | ||||
| Headache | 1.4 | 1.4 | ||
| Renal and urinary disorders | ||||
| Hematuria | 2.9 | 2.1 | ||
| Ketonuria | 2.1 | 0.7 | ||
8.3. Less Common Clinical Trial Adverse Reactions
The following treatment-related adverse drug reactions were reported infrequently (less than 1%) by patients with mild to moderate active ulcerative colitis treated with Octasa 800 mg delayed-release tablets:
Blood and lymphatic disorders: hypochromasia, leukopenia, thrombocytopenia
Cardiac disorders: bradycardia, tachycardia
Gastrointestinal disorders: dyspepsia, gastrointestinal pain, upper abdominal pain
General disorders and administration site conditions: pyrexia
Hepato-biliary disorders: hypertransaminasemia
Metabolism and nutrition disorders: hyperuricemia
Musculoskeletal and connective tissue disorders: athralgia, myalgia
Renal and urinary disorders: azotemia
Reproductive system and breast disorders: menstrual disorder
Respiratory, thoracic and mediastinal disorders: cough
Skin and subcutaneous tissue disorders: rash, rosacea
Vascular disorders: hypertension
8.5. Post-Market Adverse Reactions
In addition to the adverse events reported above in the clinical trial involving Octasa, the following adverse events have been reported in literature reports, or foreign and domestic marketing experience with Octasa or other products that contain or are metabolized to mesalazine. Because many of these events were reported voluntarily from a population of unknown size, estimates of frequency cannot be made. The relationship of the reported events to Octasa is unclear in many cases, and some may be part of the clinical presentation of ulcerative colitis.
Blood and lymphatic system disorders:
Aplastic anemia, agranulocytosis, pancytopenia, neutropenia
Immune system disorders:
Hypersensitivity reactions such as allergic exanthema, drug fever, lupus erythematosus syndrome, pancolitis
Nervous system disorders:
Paresthesia, dizziness, peripheral neuropathy, idiopathic intracranial hypertension
Cardiac disorders:
Myocarditis, pericarditis
Respiratory, thoracic and mediastinal disorders:
Allergic and fibrotic lung reactions (including dyspnoea, cough, bronchospasm, alveolitis, pulmonary eosinophilia, lung infiltration, pneumonitis), interstitial pneumonia, eosinophilic pneumonia, pleurisy, lung disorder
Gastrointestinal disorders:
Diarrhea, flatulence, nausea, vomiting, acute pancreatitis
Hepato-biliary disorders:
Changes in liver function parameters (cholestasis parameters), hepatitis, cholestatic hepatitis
Skin and subcutaneous tissue disorders:
Urticaria, pruritus, alopecia, drug reaction with eosinophilia and systemic symptoms (DRESS), photosensitivity, Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN)
Musculoskeletal, connective tissue and bone disorders:
Lupus-like syndrome with pericarditis and pleuropericarditis as prominent symptoms as well as rash and arthralgia
Renal and urinary disorders:
Impairment of renal function including acute and chronic interstitial nephritis and renal insufficiency, nephrotic syndrome, renal failure which may be reversible on early withdrawal, nephrolithiasis
Reproductive system and breast disorders:
Oligospermia (reversible)
General disorders and administration site conditions:
Intolerance to mesalazine with C-reactive protein increased and/or exacerbation of symptoms of underlying disease, chest pain
Investigations:
Blood creatinine increased, weight decreased, creatinine clearance decreased, amylase increased, red blood cell sedimentation rate increased, lipase increased, BUN increased
An unknown number of the above-mentioned undesirable effects are probably associated to the underlying inflammatory bowel disease (IBD) rather than mesalazine medication. This holds true especially for gastrointestinal undesirable effects, arthralgia, and alopecia.
To avoid blood dyscrasia resulting from developing bone marrow depression patients should be monitored with care, see 7. Warnings and Precautions.
Under co-administration of mesalazine with immunosuppressive drugs, such as azathioprine, 6-MP or thioguanine, life-threatening infections can occur, see 9. Drug Interactions.
Photosensitivity
More severe reactions are reported in patients with pre-existing skin conditions such as atopic dermatitis and atopic eczema.
Pediatric population
There is no safety experience with the use of Octasa in the pediatric population. It is expected that the target organs of possible adverse reactions in the pediatric population are the same as for adults (heart, lungs, liver, kidneys, pancreas, skin and subcutaneous tissue).
9. Drug Interactions
9.1. Serious Drug Interactions
In patients who are concomitantly treated with azathioprine, or 6-mercaptopurine or
thioguanine, a possible increase in the myelosuppressive effects of azathioprine, or 6-mercaptopurine or thioguanine should be taken into account see 9.4. Drug-Drug Interactions. As a result, life-threatening infection can occur. Patients should be closely observed for signs of infection and myelosuppression. Hematological parameters, especially the leucocyte, thrombocyte, and lymphocyte cell counts should be monitored regularly (weekly), especially at initiation of such combination therapy, see 7. Warnings and Precautions. If white blood cells are stable after 1 month, testing every 4 weeks for the following 12 weeks followed by 3 monthly monitoring intervals appears to be justified.
9.2. Drug Interactions Overview
No drug interaction studies have been performed with Octasa. There is weak evidence that mesalazine might decrease the anticoagulant effect of warfarin.
9.3. Drug-Behaviour Interactions
Interactions with behaviour have not been established.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 – Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
Azathioprine 6-Mercaptopurine | CT | Significant increases in mean whole blood 6-thioguanine nucleotide concentrations from baseline at most time points | Caution is warranted and therapeutic concentration monitoring is recommended |
Legend: CT = Clinical Trial
9.5. Drug-Food Interactions
Following concomitant food intake, a single dose of 2.4 g of mesalazine (3 Octasa delayed-release tablets) resulted in quantifiable amounts of mesalazine after 14.5 h (median tlag) compared to 4.5 h (median tlag) under fasting conditions. Thus, concomitant food intake leads to a prolongation of the median lag time of around 10 hours.
The Cmax-values of mesalazine increased 1.69-fold, and the extent of exposure (AUC0-tlast) increased 1.23-fold following concomitant food intake.
Similarly, the Cmax-values of N-acetyl mesalamine increased 1.28-fold after concomitant food intake, whereas its extent of exposure remained practically unchanged.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Several reports of possible interference with measurements, by liquid chromatography, of urinary normetanephrine causing false-positive test result have been observed in patients exposed to sulfasalazine or its metabolite, mesalazine/mesalamine/5-ASA.
10. Clinical Pharmacology
10.1. Mechanism of Action
Octasa contains mesalazine (also known as 5-aminosalicylic acid or mesalamine) which has a topical anti-inflammatory effect on the colonic mucosal cells through mechanisms that have not yet been fully clarified. Mesalazine has been shown to inhibit leukotriene B4 (LTB4) -stimulated migration of intestinal macrophages and thus may reduce intestinal inflammation by restricting migration of macrophages to inflamed areas. The production of pro-inflammatory leukotrienes (LTB4 and 5-hydroxy-6,8,11,14-eicosatetrenoic acid [5-HETE]) in macrophages of the intestinal wall is thereby inhibited. Mesalazine has been shown to activate peroxisome proliferator-activated receptor gamma (PPAR-γ) receptors which counteract nuclear activation of intestinal inflammatory responses.
10.2. Pharmacodynamics
Under trial conditions mesalazine inhibited the cyclooxygenase and thus, the release of thromboxane B2 and prostaglandin E2, but the clinical meaning of this effect is still unclear. Mesalazine inhibits the formation of platelet activating factor. Mesalazine is also an antioxidant; it has been shown to decrease formation of reactive oxygen products and to capture free radicals.
10.3. Pharmacokinetics
Table 4 – Summary of Octasa 800 mg Pharmacokinetic Parameters in healthy volunteers under fasting condition
Cmax (geometric mean) | Tmax (median) | t½ (h) (median) | AUC0-∞ (geometric mean) | CL (geometric mean) | Vd (geometric mean) | |
| Single Dose | 387.86 ng/mL | 14.0h | 17 | 7553.00 h x ng/mL | 318 L/h | 76.06 L/kg |
Absorption
Octasa tablets are coated with a pH-responsive polymer which enables the release of mesalazine only at a pH above 7, i.e. within the terminal ileum and colon. Thus mesalazine can be available to the whole colon. After any initial disruption of the coating mesalazine will continue to be released irrespective of the pH. Octasa tablets have been designed to minimize the systemic absorption of mesalazine from the digestive tract.
After a single dose of 2.4 g of mesalazine (3 Octasa 800 mg delayed-release tablets) in healthy volunteers under fasting conditions quantifiable amounts (> 2.00 ng/mL) of mesalazine were observed in plasma after 4.5 h (median tlag). The geometric mean Cmax-value of mesalazine was 387.86 ng/mL with a median tmax of 14.0 h, whereas that of N-acetyl-5-aminosalicylic acid was 971.09 ng/mL with an identical median tmax, i.e. 14.0 h.
Based on the recovery of unchanged mesalazine and the main metabolite N-acetyl-5-aminosalicylic acid in collected urine after oral fasted administration approximately 23% of the dose (more than 95% as metabolite) was excreted renally within 60 h.
Following concomitant food intake in the same study, a single dose of 2.4 g of mesalazine resulted in quantifiable amounts of mesalazine after 14.5 h (median tlag). The geometric mean Cmax-value of mesalazine was 653.56 ng/mL with a median tmax of about 30.0 h, whereas that of N-acetyl-5-aminosalicylic acid was 1245.46 ng/mL with a median tmax of 30.0 h.
Based on the recovery of unchanged mesalazine and the main metabolite N-acetyl-5-aminosalicylic acid in collected urine after oral fed administration, approximately 23% of the dose (more than 95% as metabolite) was excreted renally within 60 h.
Following concomitant food intake the Cmax-values of mesalazine increased 1.69-fold, and the extent of exposure (AUC0-tlast) increased 1.23-fold. Concerning N-acetyl-5-aminosalicylic acid after concomitant food intake the Cmax-values increased 1.28-fold, whereas its extent of exposure remained practically unchanged.
Distribution
About 43% mesalazine and about 78% N-acetyl-5-aminosalicylic acid are bound to plasma proteins. Approximately 77% of the administered dose remains in the gut lumen and the mucosal tissue. The mean apparent volume of distribution per kg of body weight (Vdw) was 147.73 L/kg (geometric mean: 76.06 L/kg) after a single dose of 2.40 g of mesalazine (3 delayed-release tablets of Octasa 800 mg) in healthy volunteers under fasting conditions. Based upon the absorption of 23.2% of the administered dose, this parameter is equal to 34.27 L/kg (geometric mean: 17.65 L/kg).
Low concentrations of mesalazine and N-acetyl-5-aminosalicylic acid have been detected in human breast milk. The clinical significance of this has not been determined.
Metabolism
Mesalazine is metabolised both by the intestinal mucosa and the liver to the inactive metabolite N-acetyl-5-aminosalicylic acid. About 96% of the drug recovered in the urine after oral administration is found as the main metabolite N-acetyl-5-aminosalicylic acid.
Elimination
The elimination of mesalazine is essentially urinary and fecal in the form of mesalazine and its N-acetyl metabolite. The geometric mean of total apparent clearance of mesalazine after administration of 2.40 g of mesalazine (3 delayed-release tablets of Octasa 800 mg) in healthy volunteers under fasting conditions was about 318 L/h (geometric mean, CV% = 137.67%, intersubject). The median elimination half-life was 17 h ranging from 10 to 50 h.
About 23% of the total dose administered was recovered in the urine within 60 h after fasted administration mainly as N-acetyl-5-aminosalicylic acid and as the parent compound (about 1%).
Special populations and conditions
- Pregnancy and breastfeeding Low concentrations of mesalazine and N-acetyl-5-aminosalicylic acid have been detected in human breast milk. The clinical significance of this has not been determined.
- Storage, Stability, and Disposal
Do not store above 25°C. Store in the original package.
Keep out of reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Mesalazine (INN, Ph. Eur., BP)
Mesalamine (USAN)
Chemical name: 5-amino-2-hydroxybenzoic acid [also known as 5-aminosalicylic acid (5-ASA)]
Molecular formula and molecular mass: C7H7NO3; 153.1
Structural formula:
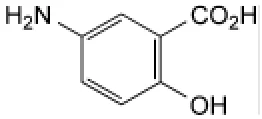
Physicochemical properties: Mesalazine is an almost white to light pink/grey/brown powder or crystals that decomposes at 280°C and is very slightly soluble in water. The pH of 2.5% aqueous suspension is 3.5-4.5. pKa value: 5.8.
Pharmaceutical standard: Mfr. Std.
14. Clinical Trials
14.1. Clinical Trials by Indication
Treatment of Moderately Active Ulcerative Colitis
TP0203 was a double blind, randomized, placebo controlled trial. Two hundred eighty one (281) male and female patients were randomly assigned to two treatment groups in a 1:1 ratio.
Adult patients (≥18 years) with a documented diagnosis of Ulcerative Colitis (UC) were eligible to participate if they met the following criteria: (1) disease extending at least 15 cm from the anal verge and (2) mildly to moderately active UC defined by a modified Ulcerative Colitis Disease Activity Index (UCDAI) score of 4 to 10 with a sigmoidoscopy component score ≥2 and a rectal bleeding component score ≥1.
One hundred forty (140) subjects received Octasa 4.8 g/day (3 x 800 mg tablets) b.i.d., and one hundred forty one (141) subjects received placebo. The study treatment was 10 weeks. All treatment regimens were orally administered, with or without food. Subjects randomized to the Octasa 4.8 g/day treatment group received three Octasa 800 mg delayed-release tablets in the morning and three Octasa 800 mg delayed-release tablets in the evening. Subjects randomized to the placebo treatment group received three placebo tablets in the morning and three placebo tablets in the evening.
Treatment and control groups were similar with respect to demographic characteristics such as age (mean 42.35 ± 14.25 years and 40.41 ± 13.80 years, respectively, range 18.5 to 79.4 years). The subjects were either Caucasian (about 80%) or Asian (about 20%) in ethnic origin. Approximately 60% of the subjects were male (Table 5).
Table 5 – Summary of Patient Demographics for Clinical Trials in Mild to Moderately Active Ulcerative Colitis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (range) | Sex |
TP0203 (ITT) | Double blind, randomised, placebo controlled | Octasa 800 mg delayed-release tablets (4.8 g/day) orally for 10 wks or placebo for 10 wks | Octasa 800 mg delayed-release tablets n=140 Placebo n=141 | Octasa 800 mg delayed-release tablets: 42.35 ± 14.25 years Placebo: 40.41 ± 13.80 years, (18.5 -79.4 years) | M/F (1:1 ratio) |
Efficacy evaluations included clinical symptoms, flexible sigmoidoscopy, determination of UC disease activity assessment index measured by the modified UC-DAI and Ulcerative Colitis Clinical Score (UCCS). Efficacy analyses were performed on the intent-to-treat (ITT) analysis set which included all randomised subjects.
The percentage of patients with mild to moderately active ulcerative colitis who were classified as a treatment success after 10 weeks of Octasa therapy based on the intent-to-treat (ITT) study population are presented in Table 6.
Table 6 – Summary of Primary Endpoints at Week 10 (Intent-to-treat population; ITT)
| Primary Endpoints | Octasa 800 mg (N=140) | Placebo (N=141) | p-value |
|---|---|---|---|
| Clinical remission at Week 10 | 57 (40.7%) | 30 (21.3%) | <0.001 |
| Endoscopic remission at Week 10 | 73 (52.1%) | 52 (36.9%) | 0.010 |
Clinical remission and endoscopic remission at Week 10 were considered as primary measures of efficacy. For the ITT population, clinical remission at Week 10 was achieved in 57 (40.7%) of the subjects who received Octasa 800 mg delayed-release tablets and 30 (21.3%) of the subjects who received placebo (p<0.001; 95% CI 8.6%, 29.6%). For endoscopic remission at Week 10, this was achieved in 73 (52.1%) of the subjects who received Octasa 800 mg delayed-release tablets and 52 (36.9%) of the subjects who received placebo (p=0.010; 95% CI 3.6%, 26.3%).
A similar trend was observed at Week 6. For the ITT population, clinical remission at Week 6 was observed in 42 (30.0%) of the subjects who received Octasa 800 mg delayed-release tablets and 29 (20.68%) of the subjects who received placebo. However, statistical significance was not achieved at Week 6 (p=0.069; 95% CI of the between group difference = [-0.7%, 19.43%]). Endoscopic remission at Week 6 was achieved in 64 (45.7%) of the subjects who received Octasa 800 mg delayed-release tablets and 35 (24.8%) of the subjects who received placebo (p<0.001; 95% CI 9.7%, 31.3%).
Results of key secondary endpoints at Week 10 (ITT) are presented in Table 7.
Table 7 - Summary of secondary endpoints at Week 10 (Intent-to-treat population; ITT)
| Secondary Endpoints | Octasa 800 mg (N=140) | Placebo (N=141) | p-value |
|---|---|---|---|
| Improvement at Week 10 | 62.9% | 40.4% | <0.001 |
| Change in modified UC-DAIa | -3.8±2.3 | -2.1±2.7 | <0.001 |
| Change in flexible proctosigmoidoscopic scorea | -0.8±0.8 | -0.5±0.7 | 0.002 |
| Change in stool frequency scorea | -0.9±0.9 | -0.3±1.1 | <0.001 |
| Change in rectal bleeding scorea | -1.0±0.8 | -0.5±0.9 | <0.001 |
| Change in PGAa | -0.8±0.9 | -0.4±0.8 | <0.001 |
| Change in UCCSa | -3.2±2.5 | -1.5±3.0 | <0.001 |
aMean±SD of change from baseline to the last post-randomization score obtained up to and including End of Treatment assessment.
Results of this clinical study (TP0203) support the efficacy of Octasa 800 mg delayed-release tablets in the treatment of patients with moderate UC for both clinical and endoscopic remission at Week 10.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General toxicology
Acute Toxicity:
Mesalazine has low acute oral toxicity, as tested in rats and dogs. The oral median lethal dose (LD50) of mesalazine in rats was determined to be 4594 mg/kg.
In dogs, the minimum dose causing emesis was 577 mg/kg. No dogs died or were sacrificed moribund up to the maximum dose tested (6000 mg/dog, equivalent to 750 mg/kg), and thus, the oral LD50 in dogs was considered to be >750 mg/kg.
Repeat-Dose Toxicity:
The principal target organs of mesalazine toxicity are the kidneys and gastrointestinal (GI) tract as determined in studies conducted in rats. In a 2-week oral toxicity study in rats, necrosis, ulceration, and inflammation in the glandular stomach were observed at doses of 360 and 1080 mg/kg/day. Renal papillary necrosis accompanied by pyelonephritis of the adjacent parenchyma was also observed at a dose of 1080 mg/kg/day. At this dose, one female animal died as a result of renal failure complicated by gastric mucosal injury. Renal papillary necrosis and gastric ulceration and inflammation have also been observed at oral doses of 360 and 480 mg/kg/day in other studies in rats, including a 4-week toxicity study, a two-year carcinogenicity study, and two reproductive toxicity studies. The no-observed-adverse-effect level (NOAEL) for the oral toxicity of mesalazine in rats was considered to be 120 mg/kg/day.
In rabbits, oral administration of mesalazine for 2 weeks at a dose of 1080 mg/kg/day resulted in reduced food consumption (females), diarrhea (males), and slight increases in urinary measurements of protein, bilirubin, acetone, and urobilinogen. No histological changes were observed in any organs at any dose level. The NOAEL for the oral toxicity of mesalazine in rabbits was determined to be 360 mg/kg/day.
In dogs, no compound-related adverse effects were observed at doses up to 2000 mg/day (175 to 200 mg/kg/day) in a 1-year oral toxicity study. In a second 1-year oral toxicity study, mucoid conjunctivitis was observed at doses of 106 mg/kg/day (1 male and 1 female) and 175 mg/kg/day (1 female), but which was considered to be a species-specific effect. No other compound-related adverse effects were observed at doses up to 2000 mg/day (175 mg/kg/day). The NOAEL for the oral toxicity of mesalazine in dogs was determined to be 175 mg/kg/day.
Genotoxicity
Mesalazine was negative for genotoxicity in in vitro genotoxicity tests, consisting of two bacterial reverse mutation tests, chromosomal aberration tests in Chinese Hamster ovary (CHO) cells and in Chinese Hamster lung fibroblast cells, a mutagenicity assay in Klebsiella pneumoniae, sister chromatid exchange assays in human lymphocytes and in CHO cells, and a micronucleus test in human lymphocytes. Mesalazine was also negative for genotoxicity in two in vivo mouse erythrocyte micronucleus tests.
Carcinogenicity
Two well-conducted carcinogenicity studies did not reveal evidence of a tumourigenic response in mice or rats, when tested at maximum tolerated dose levels of 2000 and 480 mg/kg/day, respectively.
Reproductive and developmental toxicology
In a general reproduction study in rats, oral mesalazine doses up to 480 mg/kg/day were given. No effect on fertility, gestation, viability or lactation indices, litter size, pup weight, or pup survival was seen. No mesalazine-related external or internal anomalies were noted in pups at weaning. There were also no effects on the number of viable foetuses or resorptions in dams examined on gestation day (GD) 13.
In embryo-foetal developmental studies in rats and rabbits, animals were given oral mesalazine doses up to 480 mg/kg/day. There were no compound-related effects in the total number of implantation sites, corpora lutea, pre- or post-implantation losses, resorptions, foetal viability indices, and foetal sex distribution. Mean foetal body weights were statistically significantly reduced in rats in the 480 mg/kg/day group, which was a dose that caused maternal toxicity; as such, the decrease in foetal body weights was not considered to represent a direct effect of mesalazine. Similar findings were not observed in rabbits. No compound-related teratogenicity was observed in either species.
The NOAEL for maternal toxicity was determined to be 240 mg/kg/day in rats and 480 mg/kg/day in rabbits. The NOAEL for embryo-foetal developmental toxicity (teratogenicity) was determined to be 480 mg/kg/day in rats and rabbits.
In a peri-/post-natal study in rats, animals were given oral mesalamine at doses up to 480 mg/kg/day on GD 14 through post-partum Day 21. No compound-related effects on gestation, parturition, lactation, or neonatal viability were observed. There were also no mesalazine-related external or internal anomalies observed in pups. The NOAEL for maternal toxicity was determined to be 240 mg/kg/day. The NOAEL for offspring development was considered to be 120 mg/kg/day based on the transient and minor effects on body weight observed at higher doses, which may have reflected maternal toxicity.