


Product Monograph - Octostim Liq Inj. 15mcg/mL
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Intravenous, subcutaneous | 15 mcg/mL | Hydrochloric acid, purified water, sodium chloride |
INDICATIONS AND CLINICAL USE
OCTOSTIM® (desmopressin acetate injection) is indicated for:
- The prevention of bleeding in patients with mild hemophilia A and mild von Willebrand’s disease Type I.
- The prevention or treatment of bleeding in patients with uremia.
Hemophilia A
OCTOSTIM® is indicated for patients with hemophilia A with Factor VIII levels greater than 5%.
OCTOSTIM® will often maintain hemostasis in patients with hemophilia A during surgical procedures and postoperatively, when injected 30 minutes prior to the scheduled procedure.
OCTOSTIM® will also stop bleeding in hemophilia A patients with episodes of spontaneous or trauma-induced injuries such as hemarthroses, intramuscular hematomas or mucosal bleeding.
In certain clinical situations, it may be justified to try OCTOSTIM® in patients with Factor VIII levels between 2-5%, however, these patients should be carefully monitored.
Von Willebrand’s Disease (Type I)
OCTOSTIM® is indicated for patients with mild to moderate classic von Willebrand’s Disease (Type I) with Factor VIII levels greater than 5%. OCTOSTIM® will often maintain hemostasis in surgical procedures and postoperatively when administered 30 minutes prior to the scheduled procedure.
OCTOSTIM® will usually stop bleeding in mild to moderate von Willebrand’s patients with episodes of spontaneous or trauma-induced injuries such as hemarthroses, intramuscular hematomas or mucosal bleeding.
Those von Willebrand’s disease patients who are least likely to respond are those with severe homozygous von Willebrand’s disease with Factor VIII antigen and von Willebrand’s Factor (ristocetin cofactor) activities less than 1%. Other patients may respond in a variable fashion depending on the type of molecular defect they have. Bleeding time and Factor VIII coagulant activity, Factor VIII antigen and von Willebrand’s Factor activities should be checked during administration of OCTOSTIM® to ensure that adequate levels are being achieved.
OCTOSTIM® is not indicated for the treatment of severe classic Type I von Willebrand’s disease and Type II B and when there is evidence of an abnormal molecular form of Factor VIII antigen (See CONTRAINDICATIONS.)
Other Hemostatic Disorders
OCTOSTIM® is indicated for the treatment of prolonged bleeding time in patients with uremia. It will assist in the maintenance of hemostasis in such patients during surgical procedures and post operatively when administered prior to the procedure.
Therapeutic efficacy (i.e. normalization of bleeding time) should be established in individual patients at the time of diagnosis of the bleeding disorder, or at least 72 hours prior to an elective treatment, by administration of a test dose of OCTOSTIM® (see Laboratory Tests in WARNINGS AND PRECAUTIONS section).
CONTRAINDICATIONS
OCTOSTIM® is contraindicated in patients with known hypersensitivity to desmopressin acetate or to any of the excipients.
Because of the risk of platelet aggregation and thrombocytopenia, OCTOSTIM® should not be used in patients with type II B or platelet-type (pseudo) von Willebrand’s disease.
OCTOSTIM® should not be used in patients with cardiac insufficiency, or other conditions requiring treatment with diuretic agents.
OCTOSTIM® should not be used in cases of habitual and psychogenic polydipsia, presence or a history of hyponatremia or Syndrome of Inappropriate ADH secretion (SIADH).
WARNINGS AND PRECAUTIONS
OCTOSTIM® (desmopressin acetate) treatment without concomitant restriction of water intake may lead to water retention/hyponatremia with or without accompanying signs and symptoms (reduced serum sodium, weight gain, and, in severe cases, convulsions). Other signs include persistent headache and nausea/vomiting. If these symptoms are present, serum sodium must be checked. The fluid intake should be restricted to the least possible and the body weight should be checked regularly. Should there be a gradual increase of the body weight, a decrease of serum sodium to below 130 mmol/L or plasma osmolality to below 270 mOsm/kg body weight, the fluid intake must be reduced drastically and the administration of OCTOSTIM® interrupted.
Precautions to prevent fluid overload must be taken in:
- the very young and elderly patients
- conditions characterized by fluid and/or electrolyte imbalance
- patients at risk for increased intracranial pressure
Children, elderly and patients with serum sodium levels in the lower range of normal may have an increased risk of hyponatremia.
Treatment with desmopressin should be interrupted or carefully adjusted during acute intercurrent illnesses characterized by fluid and/or electrolyte imbalance (such as systemic infections, fever, gastroenteritis), and the fluid and electrolyte balance should be carefully monitored, especially in situations with excessive bleeding.
Particular attention should be paid to the possibility of the rare occurrence of an extreme decrease in plasma osmolality that may result in seizures, which could lead to coma.
OCTOSTIM® must be used with caution in patients prone to vascular headaches, and patients with coronary insufficiency and hypertensive cardiovascular diseases because of possible changes in blood pressure and tachycardia.
Rapid infusion rates may result in severe hypotension; therefore, the speed of intravenous infusion of OCTOSTIM® should not be shorter than 20-30 minutes. A maximum dose of
0.3 mcg/kg should not be exceeded.
Lack of therapeutic effect has been noted in patients who have been febrile or otherwise “stressed” for several days. Whenever possible, therapeutic efficacy (i.e., Factor VIII response in hemophilia and bleeding time correction in other disorders) should be established in individual patients prior to use and followed throughout the course of treatment. The coincident use of anti-fibrinolytic agents to counteract desmopressin-induced plasminogen activator release has been recommended, however, benefit has not been clearly established.
The benefits of desmopressin versus other hemostatic therapies should be carefully assessed in situations where prolonged haemostasis is required including active postoperative bleeding and variceal bleeding in patients with cirrhosis.
Desmopressin should not be used routinely in the bleeding trauma patient (grade 2C). Desmopressin (0.3 mcg/kg) can be administered in patients treated with platelet-inhibiting drugs or with von Willebrand disease (Grade 2C).
The addition of desmopressin does not improve and may worsen the efficacy of terlipressin in controlling acute variceal bleeding in cirrhotic patients.
Desmopressin use is not recommended in patients with cirrhosis undergoing elective surgery or at the time of variceal bleeding (B2). Desmopressin administration in patients with cirrhosis undergoing dental extraction may be considered (B2).
OCTOSTIM® should not be used to treat patients with Type IIB von Willebrand’s disease since platelet aggregation may be induced (see CONTRAINDICATIONS).
OCTOSTIM® should not be used in patients with Hemophilia B because it has no effect on Factor IX levels.
OCTOSTIM® has no therapeutic effect in Glazmann’s thrombaesthenia.
OCTOSTIM® does not reduce prolonged bleeding time in thrombocytopenia.
Tachyphylaxis may develop with repeated use.
There have been rare reports of thrombotic events (thrombosis, cerebral thrombosis, cerebrovascular accident and disorder (stroke), acute myocardial infarction, angina pectoris and chest pain,) following desmopressin acetate injection in patients predisposed to thrombus formation. No causality has been determined; however, the drug should be used with caution in elderly patients and in patients with risk factors and history of thrombosis, thrombophilia and known cardiovascular disease.
Persistently increased endogenous Factor VIII levels are a risk factor for venous thromboembolism (VTE). The evidence for elevated vWF levels as a risk factor for VTE is less strong, but some studies have demonstrated an association.
Severe allergic reactions have been reported rarely. Fatal anaphylaxis has been reported in one patient who received intravenous OCTOSTIM®. It is not known whether antibodies to desmopressin acetate are produced after repeated administration.
OCTOSTIM® has an antidiuretic effect. Patients receiving this drug should be cautioned to reduce their ingestion of fluids for at least 6 hours after receiving the drug. Patients receiving intravenous fluids must be placed on fluid input/output monitoring.
It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when OCTOSTIM® is administered to a nursing woman.
General
Precautions must be taken in patients with moderate and severe renal insufficiency
(creatinine clearance below 50 ml/min).
Severe bladder dysfunction and outlet obstruction should be ruled out before starting treatment.
OCTOSTIM® (desmopressin acetate) produces changes in blood pressure; either an elevation or a decrease and a compensatory tachycardia. Subcutaneous administration usually results in a slight change that is transient. Greater changes may occur with intravenous infusion, especially if administered rapidly. It should, therefore, be used with caution in patients with coronary artery insufficiency and/or hypertensive cardiovascular disease.
OCTOSTIM® should not be administered to dehydrated patients until water balance has been adequately restored.
OCTOSTIM® should be used with caution in patients with cystic fibrosis because these patients are prone to hyponatremia. Children and geriatric patients should be closely observed for possible water retention due to over ingestion of fluids.
Special Populations
Pregnant Women:
There are no adequate and well-controlled studies in pregnant women. Published reports stress that, as opposed to preparations containing the natural hormone, desmopressin acetate in antidiuretic doses has no uterotonic action, but the physician will have to weigh the possible therapeutic advantage against potential danger in each case.
Reproduction studies performed in rats and rabbits have revealed no evidence of harm to the fetus due desmopressin acetate. Subcutaneous doses up to 4 times the human dose for Factor VIII stimulation on a mg/m2 basis (or 12.5 times the human dose on a mg/kg basis) and doses up to 4 times the human dose for diabetes insipidus on a mg/m2 basis (or 12.5 times the human dose on a mg/kg basis) were studied. There are several publications of management of diabetes insipidus in pregnant women with no harm to the fetus reported.
Published data on a limited number (n = 53) of exposed pregnancies in women with diabetes insipidus indicate no adverse effects of desmopressin on pregnancy or on the health of the foetus/newborn child. To date, no other relevant epidemiological data are available.
Animal studies do not indicate direct or indirect harmful effects with respect to pregnancy, embryonal/foetal development, parturition or postnatal development.
Caution should be exercised when prescribing to pregnant women.
Nursing Women:
There have been no controlled studies in nursing mothers. A single study on a post-partum woman demonstrated a marked change in plasma desmopressin acetate level following an intranasal dose of 10 mcg, but little drug was detectable in breast milk. (See WARNINGS AND PRECAUTIONS).
Results from analyses of milk from nursing mothers receiving a high dose of desmopressin (300 mcg intranasally), indicate that the amounts of desmopressin that may be transferred to the child are considerably less than the amounts required to influence diuresis.
Pediatrics
No controlled trials have been conducted in children with renal insufficiency.
Use in infants and children will require careful fluid intake restriction to prevent possible hyponatremia and water intoxication. The physician should weigh possible therapeutic advantages against potential risks in each case. No controlled trials have been conducted in infants under 3 months of age with von Willebrand’s disease or Hemophilia A thus OCTOSTIM should not be used in this patient population.
Monitoring and Laboratory Tests
Hemophilia A
Laboratory tests for assessing patient status include levels of Factor VIII coagulant, Factor VIII antigen and Factor VIII ristocetin cofactor (von Willebrand factor) as well as activated partial thromboplastin time. Factor VIII coagulant activity should be determined before giving OCTOSTIM® for hemostasis. If Factor VIII coagulant activity is present at less than 5% of normal, OCTOSTIM® should not be relied upon alone.
von Willebrand’s Disease
Laboratory tests for assessing patient status include levels of Factor VIII coagulant, Factor VIII antigen and Factor VIII ristocetin cofactor (von Willebrand factor). The skin bleeding time may be helpful in following these patients and should always be assessed pre-operatively.
Uremia
A test dose of OCTOSTIM® should be administered at the time of diagnosis of the bleeding disorder, or at least 72 hours prior to an elective treatment. The skin bleeding times should be measured before and 1 hour after OCTOSTIM® administration.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most serious adverse reaction with desmopressin is hyponatremia/water retention, which is associated with headache, nausea, vomiting, water intoxication, decreased serum sodium, weight increase, malaise, abdominal pain, muscle cramps/spasms, dizziness, decreased consciousness, confusion, generalized or local oedemas (peripheral, face), and in severe cases brain oedema, hyponatremic encephalopathy, convulsions and coma. Hyponatremia is reversible in two thirds of the adult cases reported during post-marketing. In the rest of the cases, 7% are reported as not recovered at the time when the events were reported and 21% had an unknown outcome. Treatment should be individualised and rapid overcorrection should be avoided to reduce the risk of further complications.
Post-marketing hypersensitivity reactions including local allergic reactions such as dyspnoea, erythema, generalized or local oedemas (peripheral, face), pruritus, rash, rash macular, rash maculopapular, rash erythematous, skin plaque and urticaria, have been reported in association with desmopressin injection. More serious hypersensitivity reactions including anaphylactic shock and reaction, and anaphylactoid shock and reaction have also been reported in association with desmopressin injection. Allergic reactions usually occur rapidly after drug administration and may occur during first time usage or after repeated exposure of desmopressin injection.
Rare post marketing cases of deep vein thrombosis, cerebrovascular accident/disorder (stroke), cerebral thrombosis, hypertension, pulmonary embolism, myocardial infarction, angina pectoris and chest pain have been reported in patients treated with desmopressin.
OCTOSTIM® has produced transient headache, nausea, facial flushing, tachycardia, hypotension, oliguria, abdominal cramps and vulvar pain. The frequency varies with the dosage and the route of administration.
See WARNINGS AND PRECAUTIONS for the possibility of water intoxication and hyponatremia. Very occasionally, intravenous injection of OCTOSTIM® has produced local erythema, swelling or burning pain along the course of the vein.
Side effects following intravenous administration to 297 patients included transient facial flushing (approximately 18%), fatigue (3%), headache (2%), and oliguria (1%). Other effects reported at a frequency of less than 1% included nausea, dizziness, syncope and abdominal cramping.
Side effects following subcutaneous administration to 190 subjects included transient facial flushing (7%). Other effects reported at a frequency of less than 1% included hypotension, transient headache, abdominal tension, nausea, tachycardia and discomfort at the injection site.
Side effects following intranasal administration to 78 patients included facial flushing and warmth (24%), dizziness or headache (13%), palpitations (9%), nausea (6%), fatigue (6%), red eyes (4%), decreased diuresis (3%), nasal congestion, rhinitis, tachycardia. Other effects reported at a frequency of less than 1% include abdominal cramps, allergic reactions both to desmopressin and to the preservative, somnolence.
Severe hypotension was observed in some patients who received OCTOSTIM® intravenously during cardiac surgical procedures and this may have resulted from rapid infusion rates. A dosage of 0.3 mcg/kg should not be exceeded, and the infusion rate of 20 to 30 minutes should not be exceeded.
Additional Post-Marketing Adverse Reaction Reports
The following post-marketing events have been reported:
Respiratory, thoracic and mediastinal disorders – dyspnea
Gastrointestinal disorders – nausea, vomiting
Nervous system disorders – headache, dizziness
General disorders and administration site conditions - injection/infusion site reactions including swelling, pain, extravasation, erythema, bruising and nodules, generalized or local oedemas (peripheral, face), chills
DRUG INTERACTIONS
Overview
Although the pressor activity of desmopressin acetate is very low, its use with other pressor agents should be done only with careful patient monitoring.
Desmopressin acetate injection has been used with epsilon aminocaproic acid without adverse events.
Precautions to avoid hyponatremia, including careful attention to fluid restriction and more frequent monitoring of serum sodium, must be taken in case of concomitant treatment with substances which affect water and/or sodium homeostasis, are known to release antidiuretic hormone and suspected to induce SIADH, e.g., opioids, tricyclic antidepressants, selective serotonin reuptake inhibitors, chlorpromazine, carbamazepine, antidiabetics of the sulfonylurea group particularly chlorpropamide, urea, fludrocortisone and NSAIDs, as these may cause an additive antidiuretic effect and increase the risk of water retention/hyponatremia.
Desmopressin should be used cautiously in patients who are receiving lithium, large doses of epinephrine, demeclocycline, heparin or alcohol, because the antidiuretic response to desmopressin may be decreased.
Concurrent administration of clofibrate with desmopressin reportedly potentiates and prolongs the antidiuretic effect of desmopressin.
Indomethacin may augment the magnitude but not the duration of the response to desmopressin.
DOSAGE AND ADMINISTRATION
Administration
OCTOSTIM® is administered by subcutaneous injection or as an intravenous infusion over 20 to 30 minutes to provide a dose of 0.3 mcg/kg. The maximum intravenous dose is 20 mcg. If OCTOSTIM® is used pre-operatively, it should be administered 30 minutes prior to the scheduled procedure. The peak effect is obtained one hour after administration. Response is immediate for bleeding time reduction.
Dilution for Infusion
Dilute in sterile physiological saline and infuse slowly over 20 to 30 minutes. In adults and children weighing more than 10 kg, 50 mL of diluent is used; in children weighing 10 kg or less, 10 mL of diluent is used.
The necessity for repeat administration of OCTOSTIM® or use of any blood products for hemostasis should be determined by laboratory response, as well as the clinical condition of the patient. The tendency toward tachyphylaxis (lessening of response) with repeated administration, given more frequently than every 48 hours should be considered in treating each patient.
OVERDOSAGE
OCTOSTIM® (desmopressin acetate) at excessive doses may cause headaches, abdominal cramps, nausea and facial flushing. In such cases the dosage should be reduced, frequency of administration decreased, or the drug withdrawn according to the severity of the condition. Rapid intravenous infusion may cause hypotension. A maximum intravenous dose of 0.3 mcg/kg should not be exceeded. The infusion rate of 20 to 30 minutes should not be exceeded.
There is no known specific antidote for OCTOSTIM®. Water intoxication responds rapidly to diuretic therapy (e.g., furosemide) and appropriate replacement fluid support, without interference with hemostatic effects.
Overdosage leads to a prolonged duration of action with an increased risk of fluid retention and hyponatremia.
Although the treatment of hyponatremia should be individualized, the following general recommendations can be given. Asymptomatic hyponatremia is treated with discontinuation of desmopressin treatment and fluid restriction. Infusion of isotonic or hypertonic sodium chloride may be added in cases with symptoms. When fluid retention is serious (convulsions and unconsciousness), treatment with furosemide should be added.
| For up-to-date information on the management of a suspected drug overdose, contact the Regional Poison Control Center. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
OCTOSTIM® (desmopressin acetate) is a synthetic structural analogue of the natural human hormone, arginine vasopressin with deamination of 1-cysteine and substitution of 8-L-arginine by 8-D-arginine.
OCTOSTIM® administration causes a transient increase in all components of the Factor VIII complex (Factor VIII coagulant activity, Factor VIII related antigen, and ristocetin cofactor) and in plasminogen activator. Either directly or indirectly, OCTOSTIM® causes these factors to be released very rapidly from their endothelial cell storage sites. In addition, OCTOSTIM® may have a direct effect on the vessel wall, with increased platelet spreading and adhesion at injury sites.
A second dose given before endothelial cell stores are replenished will not have as great an effect as the initial dose. Responses as great as the initial one usually are seen if 48 hours or more have elapsed between doses.
The pharmacokinetic and pharmacodynamic profiles after subcutaneous or intravenous administration to healthy volunteers are equivalent. The plasma half-life following subcutaneous and intravenous administration ranges from 3.2 to 3.6 hours.
Pharmacodynamics
Desmopressin causes a dose-dependent increase in plasma Factor VIII (antihemophilic factor), plasminogen activator, and, to a smaller degree, Factor VIII-related antigen and ristocetin cofactor activities. The mechanism by which desmopressin lowers bleeding time remains speculative.
Structural modifications of vasopressin present in desmopressin result in reduced smooth muscle contracting and vasopressor properties compared with vasopressin and lypressin. Initial studies of intranasal desmopressin at a subtherapeutic dose of 20 mcg resulted in no effect on blood pressure or pulse rate, but mean arterial pressure increases as much as 15 mm Hg were observed with doses of 40 mcg or more. In the therapeutic dose range, cardiovascular changes in normal, healthy volunteers were not considered to be clinically meaningful, but 27 of 32 volunteers had notable changes in systolic and/or diastolic blood pressure, and 8 had notable changes in pulse. Some volunteers experienced increases in diastolic blood pressure of greater than or equal to 20%; one volunteer experienced an increase in systolic blood pressure of 35% (40 mm Hg); and others experienced decreases in diastolic blood pressure, in some cases with compensatory tachycardia.
Desmopressin has been shown to interact with renal (V2) vasopressin receptors which mediate its antidiuretic effect on renal tubes. The extrarenal effects of Desmopressin in normal persons, which include stimulation of the release of Factor VIII coagulant and von Willebrand factory (ristocetin cofactor) and a decrease in blood pressure, may be mediated by interaction with receptors in other tissues which are similar to the renal V2 receptors.
Desmopressin has not been reported to stimulate uterine contractions.
Injection
Dose-response studies were performed in healthy persons, using doses of 0.1 to 0.4 mcg/kg. OCTOSTIM® provokes an average increase in Factor VIII coagulant activity two to five times baseline levels.
Plasminogen activator activity increases about threefold, after OCTOSTIM® infusion, but is of such short duration of action that there has been no clinically significant fibrinolysis in patients treated with OCTOSTIM®. The Factor VIII related antigen and ristocetin cofactor activity were also increased to a smaller degree, but still were dose dependent. The above responses reach a maximum at a point ranging from one to two hours.
The effect of repeated OCTOSTIM® administration when doses were given every 12 to 24 hours has generally shown a gradual diminution of the Factor VIII activity increase, noted with a single dose. The initial dose is reproducible in any particular patient if there are 2 or 3 days between administration, when endothelial cell storage sites are replenished.
The percentage increase of Factor VIII levels in patient with mild haemophilia A and von Willebrand’s disease was not significantly different from that observed in normal healthy individuals when treated with 0.3 mcg/kg of OCTOSTIM® infused over 10 minutes.
Desmopressin has also reportedly increased Factor VIII activity and to a lesser extent, Factor VIII related antigen and ristocetin cofactor in patients with uremia; these changes were accompanied by a shortening of bleeding time. In addition, the drug induced release into the plasma of the larger multimers of Factor VIII/von Willebrand factor in these patients.
After 300 µg of OCTOSTIM® spray, the percentage increase of Factor VIII and von Willebrand factor levels in patients with mild hemophilia A and von Willebrand’s disease was less than observed after 0.3 mcg/kg of intravenous OCTOSTIM®.
In a trial comparing intranasal and intravenous Desmopressin in patients with mild/moderate hemophilia A or von Willebrand’s disease, an intranasal dose of 300 mcg desmopressin resulted in a 54% and 75% respective increase in Factor VIII:C and von Willebrand antigen, compared to intravenous desmopressin. The mean maximum percent decrease in bleeding time following intranasal desmopressin was 1.5 times that observed following intravenous desmopressin.
A prolonged bleeding time is shortened to the same extent after doses of either 300 mcg desmopressin intranasally, or intravenous doses of 0.3 mcg/kg body weight.
Pharmacokinetics
Injection
Following IV infusion of desmopressin, the increase in plasma Factor VIII activity occurs within 15-30 minutes and peaks between 90 minutes and 3 hours after administration; the increase in Factor VIII activity is dose dependent, with a 300-400% maximum increase reportedly occurring after IV infusion of 0.4 mcg/kg dose. Plasma Factor VIII-related antigen activity has also been reported to peak within 3 hours after IV infusion of the drug. The subcutaneous route of OCTOSTIM® administered has been compared with the intravenous route in healthy volunteers and found to produce a bioequivalent response in terms of pharmacokinetic profile.
Desmopressin acetate was administered to 10 healthy volunteers in a randomized cross-over study at a dose of 0.4 mcg/kg by intravenous infusion and subcutaneous injection. The pharmacokinetic data are summarized in Table 1.
Table 1: Pharmacokinetics of OCTOSTIM after subcutaneous and intravenous administration to 10 healthy volunteers. Mean + S.D.
| Dose and route of administration | AUC (pg/h/mL-1) | Cmax (pg/mL) | Tmax (min) | Half-life (min-1) |
| 0.4 mcg/Kg i.v. | 3109 ± 1056 | 3.62 ± 0.42 | ||
0.4 mcg /Kg s.c. (4 mcg /mL ampoule) | 3492 ± 659 | 568 ± 203 | 87 ± 66 | 3.50 ± 0.39 |
0.4 mcg /Kg s.c. (40 mcg /mL ampoule) | 3164 ± 393 | 544 ± 46 | 60 ± 7 | 3.17 ± 0.33 |
Subcutaneous administration of OCTOSTIM® showed the same plasma half-life, from 3.2 to 3.6 hours, as intravenous OCTOSTIM®. The plasma profile indicates that the elimination of OCTOSTIM® from plasma follow first order kinetics. There is no significant difference in AUC between subcutaneous and intravenous OCTOSTIM®. A similar study in 14 hemophiliac patients also showed that the subcutaneous route of administration is bioequivalent to the intravenous route.
STORAGE AND STABILITY
OCTOSTIM® should be stored at refrigerator temperature 2-8°C. Do not freeze.
SPECIAL HANDLING INSTRUCTIONS
Diluted solutions
Continuous intravenous infusion
For intravenous infusion of OCTOSTIM® in adults and children weighing 10 kg or more, a dose of 0.3 mcg /kg should be drawn up into a syringe, and added to an IV bag containing 50 mL of sterile physiological saline.
For children weighing less than 10 kg, a dose of 0.3 mcg /kg should be added to 10 mL of sterile physiological saline.
It is recommended that the storage of the diluted solutions at room temperature does not exceed 24 hours.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Composition
Each mL of OCTOSTIM® contains desmopressin acetate 15 mcg, with sodium chloride and hydrochloric acid to adjust the pH to 3.5, in water for injection.
Availability
OCTOSTIM® is available in a 1 mL ampoule containing 15 mcg desmopressin. Ampoules are clear glass with a red identification ring and a blue dot indicating the cut area.
Instructions for Opening Ampoules
- 1. Hold ampoule with blue dot pointing upwards. Shake or tap ampoule to empty the tip.
- 2. With blue dot pointing upwards, snap off tip by forcing it downwards.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Desmopressin Acetate
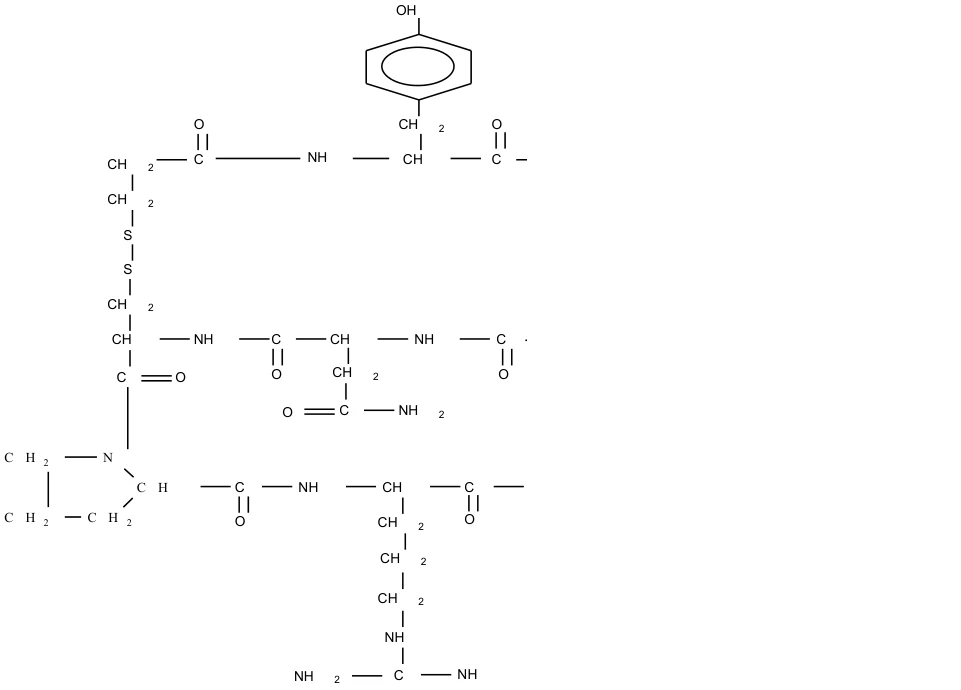
Chemical name: 1-Desamino-8-arginine-vasopressin acetate trihydrate
1-(3-mercaptopropionic acid)-8-D-arginine-vasopressin monoacetate (salt) trihydrate
Molecular formula and molecular mass:
Molecular Formula: Acetate: C48H74N14O17S2
Free Base: C46H64N14O12S2
Molecular Weight: Acetate: 1183.2
Free Base: 1069.2
Structural formula:
Physicochemical properties:
Desmopressin acetate is a white lyophilized powder which is soluble in water, methanol, ethanol, and acetic acid, and sparingly soluble in chloroform and ethyl acetate. An aqueous solution of 1 mg/mL at 24°C has a pH of 4.8.
TOXICOLOGY
Acute toxicity
The acute toxicity of desmopressin acetate is low (Table 2). Mice tolerate IV doses of 2 mg/kg. At IV doses of 30 mcg /kg in rates and 40 mcg /kg in rabbits, only transient changes in clinical behaviour were observed. Intravenous doses up to 24 mcg /kg in dogs did not produce any cardiovascular changes.
Table 2
Acute Toxicity of OCTOSTIM
| Species | Number | LD50 Dose | Route |
| Mice | 10 both sexes | <2 mg/kg | IV |
| Rats | 12 both sexes | >30 mcg /kg | IV |
| Dogs | 5 males | >24 mcg /kg | IV |
Subacute Toxicity
Results from 14-day studies show that the drug given intravenously to rates at 18 mcg //kg/day and to rabbits at 6 mcg /kg/day, causes no biologically significant changes in hemotological and clinical chemistry parameters. Post-mortem examinations did not reveal any abnormalities.
Rats which received 5 mg/kg/day subcutaneously for 3 weeks did not show any significant changes in weight, blood count, or organ changes.
Chronic Toxicity
Rat Subcutaneous Studies
In a controlled 8 week experiment, 20 rats received 2 mcg /kg/day subcutaneous desmopressin acetate. No increase in blood glucose nor morphological or histological pancreatic changes occurred.
Rats (20 per group) which received desmopressin acetate doses of 5, 50, or 500 ng/kg/day, for 6 months did not show any significant changes in weight, blood values, or levels of transaminases. The weight of heart, lungs, and kidneys decreased in female animals in the lower dose groups but not in the higher ones. In male animals, a decrease in non-esterifiable fatty acids was noted.
Dog Subcutaneous Studies
Dogs (3 per group) which received subcutaneous doses of 10 and 100 ng/kg/day desmopressin acetate for 6 months did not show any significant changes in comparison with control groups in blood sugar or transaminases and did not show histological or morphological organ changes.
Reproductive Studies
In teratogenicity testing in Wistar rats, no teratologic or embryotoxic effects were observed in 369 fetuses from 40 females dosed with up to 50 ng/kg/day desmopressin acetate subcutaneously on Day 1 through Day 20 of gestation.
In a study of 78 Dutch belted rabbits which received subcutaneous desmopressin acetate up to
10 mcg /kg/day on Day 6 through Day 18 of pregnancy, no teratogenic or embryotoxic effects were observed in 296 fetuses. Weaning was unaffected.
There have been no long-term studies in animals to assess the impairment of fertility potential of OCTOSTIM® (desmopressin acetate injection).
Carcinogenicity and Mutagenicity
There have been no long-term studies in animals to assess the carcinogenic or mutagenic potential of OCTOSTIM®.