


Product Monograph - Pegasys Rbv
SUMMARY PRODUCT INFORMATION
Information as set forth in this label only applies to PEGASYS RBV.
| Route of Administration | Dosage Form / Strength | Clinically Relevant Non-medicinal Ingredients |
| Subcutaneous | Solution in vial: 180 mcg/1.0 mL | Benzyl alcohol For a complete listing see Dosage Forms, Composition and Packaging section. |
| Subcutaneous | Solution in pre-filled syringe: 180 mcg/0.5 mL Solution in ProClick® autoinjector: 180 mcg/0.5 mL | Benzyl alcohol For a complete listing see Dosage Forms, Composition and Packaging section. |
| Oral | Tablet/200 mg | None For a complete listing see Dosage Forms, Composition and Packaging section. |
DESCRIPTION
PEGASYS RBV (peginterferon alfa-2a and ribavirin) is a combination of PEGASYS (peginterferon alfa-2a) and COPEGUS (ribavirin) tablets.
PEGASYS: Peginterferon alfa-2a is a covalent conjugate of recombinant alfa-2a interferon (approximate molecular weight [MW] 20 kD) with a single branched bis-monomethoxy polyethylene glycol (PEG) chain (approximate MW 40 kD). Interferon alfa-2a is produced biosynthetically using recombinant DNA technology, and is the product of a cloned human leukocyte interferon gene inserted into and expressed in E. coli.
COPEGUS: Ribavirin, a synthetic nucleoside analog, has shown in vitro activity against some
RNA and DNA viruses, as well as immunomodulatory activity.
INDICATIONS AND CLINICAL USE
PEGASYS RBV (peginterferon alfa-2a and ribavirin) is indicated as part of a combination regimen with other hepatitis C virus (HCV) antiviral drugs that have been authorized for combination use in Canada, or alone for the treatment of Chronic Hepatitis C in:
- Adult patients without cirrhosis
- Adult patients with compensated cirrhosis,
including HCV/HIV co-infection patients with stable HIV disease with or without antiretroviral therapy.
For HCV genotype specific treatment, see DOSAGE AND ADMINISTRATION.
Treatment with PEGASYS RBV should be initiated and monitored by a physician experienced in the management of Chronic Hepatitis C.
For information on the use of PEGASYS RBV in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
Geriatrics (> 65 years of age): Clinical studies of PEGASYS alone or in combination with COPEGUS did not include sufficient numbers of subjects aged 65 or over to determine whether they respond differently from younger subjects.
Pediatrics (< 18 years of age): PEGASYS RBV is not authorized for use in children and adolescents under the age of 18 years (see WARNINGS AND PRECAUTIONS: Special Populations, Pediatrics).
CONTRAINDICATIONS
When using in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
PEGASYS RBV (peginterferon alfa-2a and ribavirin) is contraindicated in:
- Women who are pregnant or by men whose female partners are pregnant. PEGASYS RBV should not be initiated until a report of a negative pregnancy test has been obtained immediately prior to initiation of therapy. Women of childbearing potential and their male partners must not receive PEGASYS RBV therapy unless they are using effective contraception (two reliable forms, one for each partner) during treatment with PEGASYS RBV and for the 6-month post-therapy period.
Patients who are hypersensitive to alpha interferons, E. coli-derived products, polyethylene glycol, ribavirin and/or any ingredient in the formulation or component of PEGASYS or
- COPEGUS (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
- Patients with autoimmune hepatitis and patients with decompensated cirrhosis.
- HIV-HCV patients with cirrhosis and a base-line Child-Pugh score ≥ 6, except if only the high score (≥ 6) is induced by drugs known to cause indirect hyperbilirubinemia and without evidence of clinical hepatic decompensation. (See WARNINGS AND PRECAUTIONS: Hepatic/Biliary/Pancreas and DOSAGE AND ADMINISTRATION: Special Populations).
- Patients with a history of autoimmune disease.
- Patients with hemoglobinopathies (e.g. thalassemia, sickle-cell anemia).
- Neonates and infants because the PEGASYS component contains benzyl alcohol. There have been rare reports of death in neonates and infants associated with excessive exposure to benzyl alcohol. The amount of benzyl alcohol at which toxicity or adverse effects may occur in neonates or infants is not known.
- Patients who have a pre-existing severe psychiatric condition or a history of a severe psychiatric disorder, who have pre-existing thyroid abnormalities for which thyroid function cannot be maintained in the normal range by medication, and in women who are breast feeding.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions Alpha interferons, including PEGASYS (peginterferon alfa-2a), cause or aggravate fatal or life-threatening neuropsychiatric, autoimmune, ischemic, and infectious disorders. Patients should be monitored closely with periodic clinical and laboratory evaluations. Patients with persistently severe or worsening signs or symptoms of these conditions should be withdrawn from therapy. In many cases, but not all cases, these disorders resolve after stopping interferon therapy (see WARNINGS AND PRECAUTIONS). |
General
When using in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
Ribavirins, including the COPEGUS component of PEGASYS RBV (peginterferon alfa-2a and ribavirin) may cause birth defects and/or death of the exposed fetus. COPEGUS (ribavirin) must not be used by women who are pregnant or by men whose female partners are pregnant.
In order to improve traceability of biological medicinal products, the trade name of the administered product should be clearly recorded (or stated) in the patient file.
Treatment with PEGASYS RBV should be administered under the guidance of a qualified physician and may lead to moderate to severe adverse experiences requiring dose reduction, temporary dose cessation or discontinuation of therapy.
Based on results of clinical trials, the use of ribavirin as monotherapy is not effective and COPEGUS must not be used alone.
The safety and efficacy of PEGASYS RBV have not been established in patients who have failed other alpha interferon treatments.
Patients should be informed regarding the potential benefits and risks attendant to the use of PEGASYS RBV. If home use is determined to be desirable by the physician, instructions on appropriate use should be given, including review of the contents of the Consumer Information, which does not disclose all possible adverse effects of PEGASYS RBV (see PART III: CONSUMER INFORMATION).
If home use is prescribed, patients should be thoroughly instructed in the importance of proper disposal of, and cautioned against, reuse of any needles and syringes.
Patients should be cautioned not to change to other pegylated interferons or switch to other alpha interferons without a medical consultation; changing from one interferon to another may require dosage change or adjustment.
Patients who develop dizziness, confusion, somnolence, or fatigue should be cautioned to avoid driving or operating machinery.
Cardiovascular
Because cardiac disease may be worsened by ribavirin-induced anemia, patients with a history of significant or unstable cardiac disease in the previous six months should not use the COPEGUS component of PEGASYS RBV. Cardiovascular events such as hypertension, supraventricular arrhythmias, congestive heart failure, chest pain and myocardial infarction have been associated with interferon therapies, including PEGASYS. Therefore, PEGASYS RBV should be administered with caution to patients with pre-existing cardiac disease. Patients should be assessed before initiation of therapy and should be appropriately monitored during therapy. It is recommended that patients who have pre existing cardiac abnormalities have an electrocardiogram prior to initiation of PEGASYS RBV treatment and during the course of treatment. PEGASYS RBV should not be used in patients with pre existing severe, unstable or uncontrolled cardiac disease; if there is any deterioration of cardiovascular status, PEGASYS RBV therapy should be suspended or discontinued (see WARNINGS AND PRECAUTIONS: Hematologic).
Cerebrovascular
Ischemic and hemorrhagic cerebrovascular events have been observed in patients treated with interferon alfa-based therapies, including PEGASYS. Events occurred in patients with few or no reported risk factors for stroke, including patients less than 45 years of age. Because these are spontaneous reports, estimates of frequency cannot be made and a causal relationship between interferon alfa-based therapies and these events is difficult to establish.
Dental and Periodontal Disorders
Dental and periodontal disorders, which may lead to loss of teeth, have been reported in patients receiving PEGASYS RBV. In addition, dry mouth could have a damaging effect on teeth and mucous membranes of the mouth during long-term treatment with PEGASYS RBV. Patients should brush their teeth thoroughly twice daily and have regular dental examinations. In addition some patients may experience vomiting. If this reaction occurs, they should be advised to rinse out their mouth thoroughly afterwards.
Endocrine and Metabolism
Endocrine
As with other interferons, PEGASYS may cause or aggravate hypothyroidism and hyperthyroidism. Hypoglycemia, hyperglycemia, and diabetes mellitus have been observed in patients treated with PEGASYS RBV. Patients with these conditions at baseline who cannot be effectively controlled by medication should not be started on PEGASYS RBV therapy. Patients who develop these conditions during treatment and cannot be controlled with medication should not continue PEGASYS RBV therapy.
Gastrointestinal
Colitis
Hemorrhagic/ischemic colitis, sometimes fatal, has been observed within 12 weeks of starting alpha interferon treatment. Abdominal pain, bloody diarrhea, and fever are the typical manifestations of colitis. PEGASYS RBV treatment should be discontinued immediately if these symptoms develop. The colitis usually resolves within 1 to 3 weeks following discontinuation of alpha interferon. Ulcerative colitis has also been observed in patients treated with alpha interferon.
Growth and Development (Pediatric Patients)
During the course of PEGASYS plus ribavirin therapy lasting up to 48 weeks in patients aged 5 to 17 years, weight loss and growth inhibition were common (see ADVERSE REACTIONS). At 2 years post-treatment, 16% of pediatric patients were more than 15 percentiles below their baseline weight curve and 11% were more than 15 percentiles below their baseline height curve. The available longer term data on subjects who were followed up to 6 years post-treatment is too limited to determine the risk of reduced adult height in some patients. Safety and effectiveness have not been established in patients below the age of 18 (see INDICATIONS AND CLINICAL USE and Special Populations, Pediatrics).
Hematologic
Alpha interferons, including PEGASYS, may suppress bone marrow function which may result in severe cytopenias. Very rarely alpha interferons may be associated with pancytopenia including aplastic anemia. On the other hand, the primary toxicity of the COPEGUS component is hemolytic anemia (hemoglobin < 100 g/L), which was observed in approximately 13% of PEGASYS RBV treated patients in clinical trials. The anemia associated with COPEGUS occurs within 1 to 2 weeks of initiation of therapy. Because the initial acute drop in hemoglobin may be significant, it is advised that complete blood counts (CBC) should be obtained pre-treatment and at week 2 and week 4 of therapy, or more frequently if clinically indicated. Patients should then be followed as clinically appropriate.
Extreme caution should be exercised when administering PEGASYS RBV in combination with other potentially myelosuppressive agents (see WARNINGS AND PRECAUTIONS: Monitoring and Laboratory Tests).
PEGASYS RBV should be used with caution in patients with baseline absolute neutrophil counts (ANC) < 1.5 x 10⁹/L, with baseline platelets < 90 x 109/L or baseline hemoglobin < 100 g/L. PEGASYS RBV should be discontinued, at least temporarily, in patients who develop severe decreases in ANC (< 0.5 x 10⁹/L) and/or platelet (< 25 x 109/L) counts (see DOSAGE AND ADMINISTRATION: Dose Adjustments).
If there is any deterioration of hemoglobin blood concentration, COPEGUS should be suspended or discontinued (see DOSAGE AND ADMINISTRATION: Dose Adjustments). Although ribavirin has no direct cardiovascular effects, the anemia associated with PEGASYS RBV combination therapy may result in deterioration of cardiac function and/or exacerbation of the symptoms of cardiovascular disease. If there is any deterioration of cardiovascular status, COPEGUS therapy should be suspended or discontinued (see WARNINGS AND PRECAUTIONS: Cardiovascular and DOSAGE AND ADMINISTRATION).
Pancytopenia (marked decreases in RBCs, neutrophils and platelets) and bone marrow suppression have been reported in the literature to occur within 3 to 7 weeks after the concomitant administration of ribavirin and azathioprine. This myelotoxicity was reversible within 4 to 6 weeks upon withdrawal of HCV antiviral therapy and concomitant azathioprine and did not recur upon reintroduction of either treatment alone (see DRUG INTERACTIONS).
Hepatic/Biliary/Pancreas
Hepatic
In patients who develop evidence of hepatic decompensation during treatment, PEGASYS RBV treatment should be discontinued. HIV-HCV co-infected patients with advanced cirrhosis receiving concomitant HAART may be at an increased risk of hepatic decompensation and possibly death when treated with ribavirin in combination with alpha interferons, including PEGASYS RBV. During treatment, co-infected patients should be closely monitored for signs and symptoms of hepatic decompensation (including ascites, encephalopathy, variceal bleeding, impaired hepatic synthetic function; (e.g. Child-Pugh score ≥ 6). The Child-Pugh scoring may be affected by factors related to treatment (i.e. indirect hyperbilirubinemia, decreased albumin) and not necessarily attributable to hepatic decompensation. Treatment with PEGASYS should be discontinued immediately in patients with hepatic decompensation (see DOSAGE AND ADMINISTRATION).
As with other alpha interferons, increases in ALT levels above baseline have been observed in patients treated with PEGASYS RBV, including those patients who exhibit a virological response. When the increase in ALT levels is progressive despite dose reduction or is accompanied by increased bilirubin, therapy should be discontinued (see DOSAGE AND ADMINISTRATION).
Pancreatitis
Pancreatitis, sometimes fatal, has occurred during alpha interferon treatment. PEGASYS RBV treatment should be suspended if symptoms or signs suggestive of pancreatitis are observed. PEGASYS RBV should be discontinued in patients diagnosed with pancreatitis.
HBV
The safety and efficacy of PEGASYS RBV treatment has not been established for patients with hepatitis B virus (HBV).
Hydration
Adequate hydration must be maintained in patients undergoing therapy with PEGASYS RBV, since hypotension related to fluid depletion has been seen in some patients treated with alpha interferons. Fluid replacement may be necessary.
Hypersensitivity
Serious, acute hypersensitivity reactions (e.g. urticaria, angioedema, bronchoconstriction, anaphylaxis) have been rarely observed during alpha interferon therapy and cutaneous eruptions (Stevens Johnson syndrome, toxic epidermal necrolysis) have been very rarely reported. If such a reaction develops during treatment with PEGASYS RBV, treatment should be discontinued and appropriate medical therapy should be instituted immediately. Transient rashes do not necessitate interruption of treatment.
Immune
Exacerbation of autoimmune disease including myositis, hepatitis, immune thrombocytopenic purpura (ITP), rheumatoid arthritis, interstitial nephritis, thyroiditis and systemic lupus erythematosus has been reported in patients receiving alpha interferon therapy; PEGASYS RBV is contraindicated in patients with a history of autoimmune disease. In case of appearance of psoriatic lesions and sarcoidosis, discontinuation of therapy should be considered.
Infections
While fever may be associated with the flu-like syndrome reported commonly during interferon therapy, other causes of persistent fever must be ruled out, particularly in patients with neutropenia. Serious infections (bacterial, viral, fungal) have been reported during treatment with alpha interferons including PEGASYS. Appropriate anti-infective therapy should be started immediately and discontinuation of therapy should be considered.
Ophthalmologic
As with other interferons, retinopathy including retinal hemorrhages, cotton wool spots, papilledema, retinal artery or vein obstruction and serous retinal detachment, have been reported in rare instances after treatment with PEGASYS RBV. As with other interferons, decrease or loss of vision, macular edema and optic neuritis may be induced or aggravated by PEGASYS RBV treatment. All patients should receive an eye examination at baseline. Patients with preexisting ophthalmologic disorders (e.g. diabetic or hypertensive retinopathy) should receive periodic ophthalmologic exams during PEGASYS RBV treatment. Any patient complaining of loss of visual acuity or visual field must have a prompt and complete eye examination. PEGASYS RBV treatment should be discontinued in patients who develop new or worsening ophthalmologic disorders.
Psychiatric
Severe psychiatric adverse reactions may manifest in patients receiving therapy with interferons, including PEGASYS. Depression, suicidal ideation, and suicidal attempt may occur in patients with and without previous psychiatric illness. Other CNS effects including aggressive behavior, confusion and other alterations of mental status have been observed with alpha interferons. PEGASYS RBV should be used with extreme caution in patients who report a history of depression and physicians should monitor all patients (adults and pediatrics) for evidence of depression. Physicians should inform patients of the possible development of depression prior to initiation of PEGASYS RBV therapy, and patients should report any sign or symptom of depression immediately. If severe symptoms persist, therapy should be stopped and psychiatric intervention sought (see ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION: Dose Adjustments). Safety and effectiveness have not been established in patients below the age of 18 (see INDICATIONS AND CLINICAL USE and Special Populations, Pediatrics).
Patients with Substance Use/Abuse
HCV infected patients having a co-occurring substance use disorder (alcohol, cannabis, etc.) are at an increased risk of developing psychiatric disorders or exacerbation of already existing psychiatric disorders when treated with alfa interferon. If treatment with alfa interferon is judged necessary in these patients, the presence of psychiatric co-morbidities and the potential for other substance use should be carefully assessed and adequately managed before initiating therapy. If necessary, an inter-disciplinary approach including a mental health care provider or addiction specialist should be considered to evaluate, treat and follow the patient. Patients should be closely monitored during therapy and even after treatment discontinuation. Early intervention for re-emergence or development of psychiatric disorders and substance use is recommended.
Renal
PEGASYS RBV therapy should not be initiated in patients with renal impairment, whether or not on hemodialysis, or continued if renal impairment occurs while on treatment, unless it is considered to be essential. It is recommended that renal function be evaluated in all patients prior to initiation of PEGASYS RBV therapy, preferably by estimating the patient’s creatinine clearance. PEGASYS RBV should not be administered to patients with serum creatinine > 177 µmol/L or with creatinine clearance < 0.83 mL/sec as substantial increases in ribavirin plasma concentrations are seen at the recommended dosing regimen. There are insufficient data on the safety and efficacy in such patients to support recommendations for dose adjustments. Therefore, PEGASYS RBV must be administered with extreme caution and corrective action including drug discontinuation must be considered if adverse events develop (see DOSAGE AND ADMINISTRATION: Dose Adjustments and ACTION AND CLINICAL PHARMACOLOGY: Pharmacokinetics of PEGASYS RBV in Special Populations).
Respiratory
As with other alpha interferons, pulmonary symptoms, including dyspnea, pulmonary infiltrates, pneumonia, pneumonitis, including fatality, and pulmonary hypertension have been reported during therapy with PEGASYS RBV. Any patient developing fever, cough, and dyspnea or other respiratory symptoms must have a chest X-ray taken. If there is evidence of persistent or unexplained pulmonary infiltrates or pulmonary function impairment, treatment should be discontinued. PEGASYS RBV should not be administered to patients with chronic obstructive pulmonary disease (COPD).
Sexual Function/Reproduction
Reproduction
Ribavirin accumulates intracellularly and is cleared from the body very slowly. It is not known whether ribavirin contained in sperm will exert a potential teratogenic effect upon fertilization of the ova. Therefore, men must be instructed to use a condom to minimize delivery of ribavirin to their female partners. Male patients and their female partners of childbearing age must practice effective contraception (two reliable forms, one for each partner) during ribavirin therapy and for 6 months (based on the half-life of ribavirin of 12 days when the drug is administered at multiple doses) after treatment has stopped (see Pharmacokinetics of COPEGUS).
Evaluation of experimental animal studies showed reproductive toxicity. Significant teratogenic and/or embryocidal potential have been demonstrated for ribavirin in all animal species in which adequate studies have been conducted, occurring at doses well below the recommended human dose. Malformations of the skull, palate, eye, jaw, limbs, skeleton and gastrointestinal tract were noted. The incidence and severity of teratogenic effects increased with escalation of the ribavirin dose. Survival of fetuses and offspring was reduced.
Peginterferon alfa-2a has not been studied for its teratogenic effect. Treatment with interferon alfa-2a resulted in a statistically significant increase in abortifacient activity in rhesus monkeys; no teratogenic effects were seen in the offspring delivered at term (see Special Populations: Pregnant Women).
Transplantation
Organ Transplant Recipients: The safety and efficacy of PEGASYS RBV treatment have not been established in patients with liver or other transplantations. As with other alpha interferons, liver and renal graft rejections have been reported on PEGASYS, alone or in combination with COPEGUS.
Special Populations
Pregnant Women: Ribavirins, including the COPEGUS component of PEGASYS RBV may cause birth defects and/or death of the exposed fetus. COPEGUS must not be used by women who are pregnant or by men whose female partners are pregnant.
PEGASYS RBV therapy must not be initiated until a report of a negative pregnancy test has been obtained immediately prior to initiation of therapy. Females of childbearing potential and males with female partners receiving PEGASYS RBV must be advised of the teratogenic/ embryocidal risks and must be instructed to use two forms of effective contraception (two reliable forms, one for each partner) during treatment and for 6 months after treatment has concluded. Routine monthly pregnancy tests must be performed during this time (see CONTRAINDICATIONS). Patients should be advised to notify the physician immediately in the event of a pregnancy. If pregnancy does occur during treatment or within six months from stopping treatment, the patient must be advised of the significant teratogenic risk of ribavirin to the fetus (see Sexual Function/Reproduction: Reproduction).
As with other alpha interferons, women of childbearing potential receiving PEGASYS therapy should be advised to use effective contraception during therapy (see Sexual Function/
Reproduction: Reproduction).
Nursing Women: It is not known whether the components of PEGASYS RBV are excreted in human milk. Because many drugs are excreted in human milk and to avoid any potential for serious adverse reactions in nursing infants from PEGASYS RBV, nursing must be discontinued prior to the start of PEGASYS RBV therapy.
Pediatrics (< 18 years of age): Safety and effectiveness of PEGASYS RBV have not been established in patients below the age of 18. Therefore, PEGASYS RBV is not recommended for use in children and adolescents under the age of 18 years (see also INDICATIONS AND CLINICAL USE and WARNINGS AND PRECAUTIONS: Growth and Development (Pediatric Patients)).
Geriatrics (> 65 years of age): Clinical studies of PEGASYS alone or in combination with COPEGUS did not include sufficient numbers of subjects aged 65 or over to determine whether they respond differently from younger subjects.
Monitoring and Laboratory Tests
Before beginning PEGASYS RBV combination therapy, standard hematological and biochemical profiles should be obtained for all patients. After initiation of therapy, hematological tests should be performed at 2 and 4 weeks and biochemical tests should be performed at 4 weeks. Additional testing should be performed periodically during therapy.
The enrolment criteria used for the clinical studies of PEGASYS RBV may be considered as a guideline to acceptable baseline values for initiation of treatment:
- Platelet count ≥ 90 x 109/L (75 x 109/L in patients with cirrhosis or transition to cirrhosis)
- ANC ≥ 1.5 x 10⁹/L
- Serum creatinine concentration < 1.5 x upper limit of normal
- TSH and T4 within normal limits or adequately controlled thyroid function.
- HIV-HCV co-infection: CD4+ ≥ 200/µl or CD4+ ≥ 100/µl - < 200/µl and HIV-1 RNA < 5000 copies/mL using Amplicor HIV-1 Monitor Test, v 1.5.
PEGASYS RBV treatment was associated with decreases in both total white blood cell (WBC) count and ANC, usually starting within the first 2 weeks of treatment (see ADVERSE REACTIONS). In clinical studies, progressive decreases thereafter were infrequent. PEGASYS dose reduction is recommended when ANC decreases to levels below 0.75 x 10⁹/L (see DOSAGE AND ADMINISTRATION: Dose Adjustments). For patients with ANC values below 0.5 x 10⁹/L treatment should be suspended until ANC values return to more than 1.0 x 10⁹/L. In clinical trials with PEGASYS RBV, the decrease in ANC was reversible upon dose reduction of PEGASYS or cessation of therapy.
PEGASYS RBV treatment was associated with decreases in platelet count, which returned to pre-treatment (baseline) levels during the post-treatment observation period (see ADVERSE REACTIONS). PEGASYS dose reduction is recommended when platelet count decreases to levels below 50 x 109/L, and discontinuation of therapy is recommended when platelet count decreases to levels below 25 x 109/L (see DOSAGE AND ADMINISTRATION: Dose Adjustments).
The maximum drop in hemoglobin usually occurred during the first 8 weeks of initiation of PEGASYS RBV therapy. Because of this initial acute drop in hemoglobin, it is advised that a complete blood count should be obtained pretreatment and at week 2 and week 4 of therapy or more frequently if clinically indicated. Additional testing should be performed periodically during therapy. Patients should then be followed as clinically appropriate.
Pregnancy Tests: Monthly pregnancy testing must be done during PEGASYS RBV combination therapy and for 6 months after discontinuing therapy in female patients and female partners of male patients.
Thyroid Changes: The occurrence of thyroid function abnormalities or the worsening of pre-existing thyroid disorders has been reported with the use of alpha interferon therapies, including PEGASYS RBV. Discontinuation of therapy should be considered in patients whose thyroid abnormalities cannot be adequately treated.
ADVERSE REACTIONS
The adverse reactions observed with other alpha interferons and ribavirin may be expected with PEGASYS (peginterferon alfa-2a) and PEGASYS RBV (peginterferon alfa-2a and ribavirin).
When using in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
Adverse Drug Reaction Overview
The frequency and severity of the most commonly reported adverse reactions are similar in patients treated with PEGASYS RBV combination therapy and interferon alfa-2b plus ribavirin. Flu like illness (rigors, pyrexia, myalgia), depression, insomnia, irritability, and alopecia were reported less frequently with PEGASYS RBV than with interferon alfa-2b plus ribavirin (> 5% difference between treatment groups). The most frequently reported adverse reactions with PEGASYS RBV combination therapy were mostly mild to moderate in severity and were manageable without the need for discontinuation of therapy.
Clinical Trial Adverse Drug Reactions
Chronic Hepatitis C Mono-infection
In mono-infected clinical trials, the incidence of withdrawal from treatment for all patients due to adverse events and laboratory abnormalities was 9% for PEGASYS monotherapy and 13% for PEGASYS RBV combination therapy. Respectively, only 1% or 3% of patients required discontinuation of either PEGASYS or PEGASYS RBV combination therapy due to laboratory abnormalities. Treatment-limiting events including serious and severe adverse events and adverse events and laboratory abnormalities leading to premature withdrawal or requiring dose modification with the combination treatment occurred with the lowest frequency in patients receiving 24 weeks of treatment and the 800 mg dose of COPEGUS.
HIV-HCV Co-infection
In HIV-HCV co-infected patients, the clinical adverse events reported on PEGASYS, PEGASYS RBV and interferon alfa-2a plus ribavirin were similar to that observed in HCV mono-infected patients.
In the co-infection study, the incidence of withdrawal from treatment for clinical adverse events, laboratory abnormalities or AIDS-defining events was 16% for PEGASYS monotherapy and 15% for both PEGASYS RBV and interferon alfa-2a plus ribavirin given for 48 weeks. Respectively, 4%, 3% or 1% of patients required discontinuation of PEGASYS or PEGASYS RBV or interferon alfa-2a plus ribavirin for laboratory abnormalities. In PEGASYS RBV combination therapy, the PEGASYS dose modification occurred in 39%, and the COPEGUS dose modification occurred in 37%, of the co-infected patients. In interferon alfa-2a plus ribavirin therapy, the interferon alfa-2a dose modification occurred in 16%, and the COPEGUS dose modification occurred in 28%, of the co-infected patients. In PEGASYS monotherapy, PEGASYS dose modification occurred in 38% of the co-infected patients. Serious adverse events were reported in 21%, 17% and 15% of those receiving PEGASYS monotherapy, PEGASYS RBV or interferon alfa-2a plus ribavirin, respectively.
Limited safety data (N= 31) is available in co-infected patients with CD4+ cell counts <200/µl treated with PEGASYS and PEGASYS RBV. PEGASYS containing treatment was associated with an on-treatment reduction in absolute CD4+ cell count without a reduction in CD4+ cell percentage. CD4+ cell count indices returned to baseline values during the follow-up period of the study. PEGASYS containing treatment had no apparent negative impact on the control of HIV viremia during therapy or follow-up.
Because clinical trials are conducted under very specific conditions the adverse drug reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 1a Adverse Reactions ( ≥ 5% of Incidence in Any Treatment Group).
| HCV | HIV-HCV | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Body System | Interferon alfa-2b 3MIU + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 24 weeks | INF alfa-2a 3MIU + ribavirin 800 mg 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 48 weeks | ||||||||||||||
| N=443a | N=887b | N=207c | N=285d | N=288d | |||||||||||||||
| % | % | % | % | % | |||||||||||||||
| Endocrine Disorders | |||||||||||||||||||
| Hypothyroidism | 5 | 4 | 2 | 1 | <1 | ||||||||||||||
| Gastrointestinal | |||||||||||||||||||
| Nausea | 28 | 28 | 29 | 19 | 24 | ||||||||||||||
| Diarrhea | 10 | 14 | 15 | 10 | 16 | ||||||||||||||
| HCV | HIV-HCV |
|---|
| Body System | Interferon alfa-2b 3MIU + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 24 weeks | INF alfa-2a 3MIU + ribavirin 800 mg 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 48 weeks |
|---|
| N=443a | N=887b | N=207c | N=285d | N=288d |
|---|
| % | % | % | % | % | |
|---|---|---|---|---|---|
| Abdominal pain | 9 | 10 | 9 | 7 | 7 |
| Dry mouth | 7 | 6 | 8 | 2 | 5 |
| Nausea and vomiting | 6 | 7 | 8 | 8 | 8 |
| Dyspepsia | 5 | 6 | 2 | 6 | 4 |
| General | |||||
| Fatigue | 53 | 49 | 45 | 36 | 40 |
| Pyrexia | 54 | 39 | 37 | 32 | 41 |
| Rigors | 34 | 25 | 30 | 17 | 16 |
| Injection site reaction | 16 | 21 | 28 | 8 | 10 |
| Asthenia | 16 | 15 | 18 | 23 | 26 |
| Pain | 9 | 10 | 9 | 4 | 6 |
| Malaise | 3 | 4 | 3 | 7 | 6 |
| Metabolic and Nutritional | |||||
| Anorexia | 26 | 27 | 20 | 25 | 23 |
| Weight decrease | 10 | 7 | 2 | 13 | 16 |
| Appetite decrease | - | - | - | 9 | 7 |
| Musculoskeletal, Connective Tissue and Bone | |||||
| Myalgia | 49 | 38 | 42 | 27 | 32 |
| Arthralgia | 23 | 22 | 20 | 13 | 16 |
| Back pain | 5 | 5 | 3 | 3 | 3 |
| Neurological | |||||
| Headache | 49 | 47 | 48 | 34 | 35 |
| Insomnia | 37 | 32 | 30 | 23 | 19 |
| Dizziness (excluding vertigo) | 14 | 15 | 13 | 9 | 7 |
| Concentration impairment | 13 | 10 | 8 | 2 | 2 |
| Memory impairment | 5 | 5 | 4 | <1 | 1 |
| Psychiatric | |||||
| Depression | 28 | 21 | 17 | 20 | 22 |
| Irritability | 27 | 24 | 28 | 17 | 15 |
| Anxiety | 12 | 8 | 8 | 7 | 8 |
| Mood alteration | 6 | 6 | 8 | 2 | <1 |
| Emotional disorders | 4 | 5 | 5 | 1 | <1 |
| Libido decreased | 3 | 3 | 5 | 1 | 2 |
| Nervousness | 5 | 3 | - | 1 | 1 |
| Respiratory, Thoracic and Mediastinal | |||||
| Dyspnea | 14 | 13 | 11 | 3 | 7 |
| Cough | 7 | 13 | 8 | 2 | 3 |
| Dyspnea (exertional) | 7 | 4 | 3 | 2 | 3 |
| Skin and Subcutaneous Tissue | |||||
| Alopecia | 33 | 24 | 25 | 5 | 10 |
| Pruritus | 18 | 21 | 25 | 3 | 4 |
| Dermatitis | 13 | 16 | 15 | <1 | 1 |
| Dry Skin | 13 | 12 | 13 | 4 | 4 |
| Rash | 5 | 9 | 7 | 5 | 5 |
| Sweating increased | 5 | 5 | 2 | 2 | 5 |
| HCV | HIV-HCV |
|---|
| Body System | Interferon alfa-2b 3MIU + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 1000 or 1200 mg ribavirin 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 24 weeks | INF alfa-2a 3MIU + ribavirin 800 mg 48 weeks | PEGASYS 180 mcg + 800 mg ribavirin 48 weeks |
|---|
| N=443a | N=887b | N=207c | N=285d | N=288d |
|---|
| % | % | % | % | % | |
|---|---|---|---|---|---|
a Data from study 1 b Pooled data from studies 1 and 2 c Data from study 2 d Data from study 3 | |||||
Table 1b Adverse reactions reported in ≥ 1% to < 5% on PEGASYS RBV combination or PEGASYS monotherapy in patients in clinical trials were:
| Any Treatment Group | HIV-HCV Only | |
|---|---|---|
| Body system | Common ≥ 1% to < 5% | Other adverse reactions ≥ 1% to ≤ 3% |
| Blood and lymphatic system disorders | lymphadenopathy, thrombocytopenia | |
| Cardiac disorders | palpitations,oedema peripheral, tachycardia | |
| Ear and labyrinth disorders | vertigo, earache, tinnitus | |
| Endocrine disorders | hyperthyroidism | |
| Eye disorders | vision blurred, eye inflammation, xerophthalmia, eye pain | |
| Gastrointestinal disorders | mouth ulceration, flatulence, gingival bleeding, stomatitis, constipation, dysphagia, glossitis | cheilitis |
| General disorders and administration site conditions | lethargy, chest pain, hot flushes, thirst, influenza-like illness | |
| Infections and infestations | herpes simplex, URI infection, bronchitis, oral candidiasis | influenza, pneumonia |
| Injury and poisoning | substance abuse | |
| Metabolism and nutrition disorders | dehydration | hyperlactacidemia /lactic acidosis |
| Musculoskeletal, connective tissue and bone disorders | muscle cramps, neck pain, musculoskeletal pain, bone pain, arthritis, muscle weakness | |
| Nervous system disorders | taste disturbance, weakness, paraesthesia, hypoaesthesia, tremor , migraine, somnolence, hyperaesthesia, nightmares, syncope | |
| Psychiatric disorders | aggression, suicidal ideation, confusional state | affect lability, apathy |
| Renal and urinary disorders | chromaturia | |
| Reproductive system and breast disorders | impotence | |
| Respiratory, thoracic and mediastinal disorders | sore throat, pharyngolaryngeal pain, epistaxis, nasopharyngitis, sinus congestion, rhinitis, nasal congestion | |
| Skin and subcutaneous tissue disorders | eczema, night sweats, psoriasis, photosensitivity reaction, urticaria, skin disorder | acquired lipodystrophy |
| Vascular disorders | flushing, hypertension |
As with other alpha interferon therapies, uncommon to rare cases (< 1%) of the following serious adverse events have been reported in patients receiving PEGASYS RBV combination or PEGASYS monotherapy during clinical trials:
Blood and the lymphatic system disorders: thrombotic thrombocytopenic purpura (TTP)
Cardiac disorders: arrhythmia, atrial fibrillation, pericarditis
Eye disorders: corneal ulcer
Gastrointestinal disorders: peptic ulcer, gastrointestinal bleeding, pancreatitis, abdominal distention
Immune system disorders: autoimmune phenomena (e.g. ITP, thyroiditis, psoriasis, rheumatoid arthritis, SLE), sarcoidosis
Infections and Infestations: skin infection, otitis externa, endocarditis
Hepato-biliary: hepatic dysfunction, fatty liver, cholangitis, malignant hepatic neoplasm
Nervous system disorders: myositis, peripheral neuropathy*, coma
Psychiatric disorders: suicide, panic attack, psychotic disorder, hallucination
Respiratory, thoracic and mediastinal disorders: interstitial pneumonitis with fatal outcome, pulmonary embolism
Vascular disorders: cerebral hemorrhage
Rarely, alpha interferon including PEGASYS RBV or PEGASYS monotherapy may be associated with pancytopenia, and very rarely, aplastic anemia has been reported.
Uncommon to very rare cases of hearing impairment (deafness) have been reported.
* In protocol NR15961 (HIV-HCV) the frequency was reported as 2% in the PEGASYS monotherapy arm.
Chronic Hepatitis C Pediatric Patients
In a clinical study, pediatric subjects treated with PEGASYS plus ribavirin combination therapy showed a delay in weight and height increases after 48 weeks of therapy compared with baseline. Both weight and height for age z-scores as well as the percentiles of the normative population for subject weight and height decreased during treatment. At the end of 2 years follow-up after treatment, most subjects had returned to baseline normative curve percentiles for weight (64th mean percentile at baseline, 60th mean percentile at 2 years post-treatment) and height (54th mean percentile at baseline, 56th mean percentile at 2 years post-treatment). At the end of treatment, 43% (23 of 53) of subjects experienced a weight percentile decrease of more than 15 percentiles, and 25% (13 of 53) experienced a height percentile decrease of more than 15 percentiles on the normative growth curves. At 2 years post-treatment, 16% (6 of 38) of subjects were more than 15 percentiles below their baseline weight curve and 11% (4 of 38) were more than 15 percentiles below their baseline height curve.
55% (21 of 38) of subjects who completed the original study enrolled in the long-term follow up extending up to 6 years post-treatment. The study demonstrated that the post-treatment recovery in growth at 2 years post-treatment was maintained to 6 years post-treatment. Of the 4 subjects who were more than 15 percentiles below their baseline height curve at 2 years post-treatment, 2 entered the long-term follow-up study. They either returned to baseline comparable height percentiles at 6 years post-treatment (n=1) or a non-treatment related causative factor has been identified (n=1). The available longer term data on subjects who were followed up to 6 years post-treatment is limited to determine the risk of reduced adult height in some patients. Safety and effectiveness have not been established in patients below the age of 18 (see INDICATIONS AND CLINICAL USE and Special Populations, Pediatrics).
Abnormal Hematologic and Clinical Chemistry Findings
Hematology
As with other interferon therapies, treatment with PEGASYS monotherapy and PEGASYS RBV combination therapy was associated with decreases in hematological values, which generally improved with dosage modification and returned to pretreatment levels within 4 to 8 weeks upon cessation of therapy (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Although hematological toxicities of neutropenia, thrombocytopenia and anemia occurred more frequently in HIV-HCV patients, the majority could be managed by dose modification and the use of growth factors and infrequently required premature discontinuation of treatment.
Hemoglobin: Treatment with PEGASYS monotherapy for HCV was associated with small gradual decrease in hemoglobin and hematocrit. Less than 1% of all patients treated with PEGASYS, including those with cirrhosis, required dose modification for anemia (< 100 g/L). No patients receiving interferon alfa-2a required anemia-related dose modifications, due to drops in hemoglobin levels. Anemia due to hemolysis is the most significant toxicity of ribavirin therapy. Anemia (hemoglobin < 100 g/L) was observed in 13% of PEGASYS RBV combination-treated patients in HCV clinical trials. The maximum drop in hemoglobin occurred during the first 8 weeks of initiation of ribavirin therapy (see DOSAGE AND ADMINISTRATION: Dose Adjustments).
Approximately 10% of patients on PEGASYS RBV combination therapy required COPEGUS dose modification for anemia. Patients receiving 800 mg of COPEGUS for 24 weeks had the lowest frequency of decrease in hemoglobin levels to < 100 g/L; hemoglobin levels did not fall to < 85 g/L in any of these patients.
Anemia (hemoglobin < 100g/L) was reported in 8% and 14% of HIV-HCV co-infected patients treated with PEGASYS monotherapy or PEGASYS RBV combination therapy, respectively.
White Blood Cells: Treatment with PEGASYS for HCV was associated with decreases in values for both total WBC and ANC. Approximately 4% and 5% of patients on PEGASYS monotherapy or PEGASYS RBV combination therapy, respectively, had transient decreases in ANC to levels below 0.5 x 10⁹/L at some time during therapy.
In HIV-HCV co-infected patients, 13% and 11% of those receiving PEGASYS monotherapy and PEGASYS RBV combination therapy, respectively, had decreases in ANC levels below 0.5 x 10⁹/L.
Platelet Count: Treatment with PEGASYS was associated with decreases in values for platelet counts. In HCV clinical trials, approximately 5% of patients had decreases in platelet counts to levels below 50 x 109/L. Most of these patients were cirrhotic at baseline and/or entered the study with a baseline platelet count as low as 75 x 109/L.
Table 2
Interferon alfa-2b 3MIU + 1000 or 1200 mg ribavirin 48 wk | Peginterferon alfa-2a 180 mcg + 1000 or 1200 mg ribavirin 48 wk | Peginterferon alfa-2a 180 mcg + 800 mg ribavirin 24 weeks | |||||||
N=443a % | N=887b % | N=207c % | |||||||
| Hemoglobin level (< 100 g/L) | 10.8 | 13 | 3.4 | ||||||
| ANC (< 0.5 x 10⁹/L ) | 1.1 | 5 | 3.4 | ||||||
| Platelet counts (< 50 x 109/L) | 0.2 | 5 | 3.9 | ||||||
a Data from study 1
b Pooled data from studies 1 and 2
c Data from study 2
In HIV-HCV patients, 10% and 8% of those receiving PEGASYS monotherapy and PEGASYS RBV combination therapy, respectively, had decreases in platelets below 50 x 109/L.
Clinical Chemistry
Thyroid Function: PEGASYS treatments was associated with clinically significant abnormalities in thyroid laboratory values requiring clinical intervention (see WARNINGS AND PRECAUTIONS: Monitoring and Laboratory Tests). The frequencies observed with PEGASYS treatments were similar to those observed with other interferons.
Triglycerides: Triglyceride levels are found to be elevated in patients receiving alpha interferon therapy, including PEGASYS.
For a full listing of PEGASYS monotherapy adverse reactions, please refer to the current PEGASYS product monograph.
Post-marketing
During the post-marketing period, erythema multiforme, Stevens-Johnson Syndrome, toxic epidermal necrolysis, pure red cell aplasia (PRCA) and homicidal ideation have been reported very rarely with PEGASYS RBV combination therapy.
Dehydration has been reported rarely with PEGASYS RBV combination therapy.
As with other alpha interferons, serous retinal detachment has been reported with PEGASYS RBV combination therapy.
As with other alpha interferons, liver and renal graft rejections have been reported on PEGASYS, alone or in combination with COPEGUS.
Adverse reactions reported in a post-marketing setting are: tongue pigmentation and seizures.
DRUG INTERACTIONS
Overview
When using in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
No pharmacokinetic interactions between PEGASYS (peginterferon alfa-2a) and COPEGUS (ribavirin) have been observed in HCV clinical trials in which PEGASYS was used in combination with ribavirin.
PEGASYS: Treatment with 180 mcg PEGASYS once weekly for 4 weeks had no effect on the pharmacokinetic profiles of tolbutamide (CYP 2C9), mephenytoin (CYP 2C19), debrisoquine (CYP 2D6), and dapsone (CYP 3A4) in healthy male subjects.
COPEGUS: Results of in vitro studies using both human and rat liver microsome preparations indicated no cytochrome P450 enzyme mediated metabolism of ribavirin. Ribavirin does not inhibit cytochrome P450 enzymes. There is no evidence from toxicity studies that ribavirin induces liver enzymes. Therefore, there is a minimal potential for P450 enzyme- based interactions.
The bioavailability of ribavirin 600 mg was decreased by co-administration with an antacid containing magnesium, aluminium and methicone; AUCtf decreased 14%. It is possible that the decreased bioavailability in this study was due to delayed transit of ribavirin or modified pH. This interaction is not considered to be clinically relevant.
Any potential for interactions may persist for up to 2 months (5 half-lives for ribavirin) after cessation of ribavirin therapy due to the long half-life.
Drug-Drug Interactions
Table 3 Established or Potential Drug-Drug Interactions
| Proper name | Ref | Effect | Clinical comment |
|---|
| Proper name | Ref | Effect | Clinical comment |
|---|---|---|---|
Peginterferon alfa-2a and Methadone | CT | In a pharmacokinetic study of 24 HCV patients concomitantly receiving methadone maintenance therapy (median dose 95mg; range 30 mg to 150 mg), treatment with PEGASYS 180μg sc once weekly for 4 weeks was associated with mean methadone levels that were 10% to 15% higher than at baseline. | The clinical significance of this finding is unknown; nonetheless, patients should be monitored for the signs and symptoms of methadone toxicity. |
Peginterferon alfa-2a and Theophylline | T | PEGASYS is a modest inhibitor of cytochrome P450 1A2: a 25% increase in theophylline’s AUC was observed in the same study. Comparable effects on the pharmacokinetics of theophylline have been seen after treatment with standard alpha interferons. Alpha interferons have been shown to affect the oxidative metabolism of some drugs by reducing the activity of hepatic microsomal cytochrome P450 enzymes. | Theophylline serum concentrations should be monitored and appropriate dose adjustments of theophylline made for patients taking theophylline and PEGASYS concomitantly. |
Ribavirin and Didanosine | CT | Ribavirin potentiated the antiretroviral effect of didanosine (ddI) in vitro and in animals by increasing the formation of the active triphosphate anabolite (ddATP). This observation also raised the possibility that concomitant administration of ribavirin and ddI might increase the risk of adverse reactions related to ddI (such as peripheral neuropathy, pancreatitis, and hepatic steatosis with lactic acidosis). While the clinical significance of these findings is unknown, one study of concomitant ribavirin and ddI in patients with HIV disease did not result in further reductions in viraemia or an increase in adverse reactions. Plasma pharmacokinetics of ddI were not significantly affected by concomitant ribavirin in this study, although intracellular ddATP was not measured. Exposure to didanosine or its active metabolite (dideoxyadenosine 5’-triphosphate) is increased when didanosine is co-administered with ribavirin. | Co-administration of ribavirin and didanosine is not recommended. Reports of fatal hepatic failure, as well as, peripheral neuropathy, pancreatitis, and symptomatic hyperlactatemia/lactic acidosis have been reported. |
| Proper name | Ref | Effect | Clinical comment |
|---|---|---|---|
Ribavirin and Lamivudine, Stavudine, Zidovudine. | T CT | Ribavirin was shown in-vitro to inhibit phosphorylation of zidovudine and stavudine. The clinical significance of these findings is unknown. However, these in-vitro findings raise the possibility that concurrent use of ribavirin with either zidovudine or stavudine might lead to increased HIV plasma viremia. No evidence of drug interaction was observed in 47 HIV-HCV co-infected patients who completed a 12 week pharmacokinetic substudy to examine the effect of ribavirin on the intracellular phosphorylation of some nucleoside reverse transcriptase inhibitors (lamivudine, zidovudine, or stavudine). | Therefore, it is recommended that plasma HIV RNA levels be closely monitored in patients treated with ribavirin concurrently with either of these two agents. If HIV RNA levels increase, the use of ribavirin concomitantly with reverse transcriptase inhibitors must be reviewed. Plasma exposure of ribavirin did not appear to be affected by concomitant administration of NRTIs. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Peginterferon alfa-2a and telbivudine
A non-Roche sponsored pilot clinical trial in Hepatitis B investigating the combination of telbivudine 600 mg daily, with pegylated interferon alfa -2a, 180 micrograms once weekly by subcutaneous administration, indicated that this combination is associated with an increased risk for developing serious peripheral neuropathy at a rate of 10%. An increased risk can not be ruled out for combination treatment with other interferon products (pegylated or standard). The benefit of telbivudine in combination with interferon alfa (pegylated or standard) is not currently established in patients. It is not recommended that telbivudine be given in combination with PEGASYS.
Azathioprine:
Ribavirin, by having an inhibitory effect on inosine monophosphate dehydrogenase, may interfere with azathioprine metabolism possibly leading to an accumulation of 6-methylthioinosine monophosphate (6-MTIMP), which has been associated with myelotoxicity in patients treated with azathioprine.
In individual cases where the benefit of administering ribavirin concomitantly with azathioprine warrants the potential risk, it is recommended that close hematologic monitoring be done during concomitant azathioprine use to identify signs of myelotoxicity, at which time treatment with these drugs should be stopped (see WARNINGS AND PRECAUTIONS, Hematologic).
Drug-Herb Interactions
Pulmonary symptoms have been reported more frequently when sho-saiko-to, a Chinese herbal medicine, also known as Xiao-Chai-Hu was given with interferon alfa-2a. This herb should not be taken by patients receiving interferon.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
When using PEGASYS RBV in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs for specific dosage and administration instructions pertaining to those products.
Dosing Considerations
Substitution by any other biological medicinal product requires the consent of the prescribing physician.
Treatment should be individualized to the patient depending on baseline disease characteristics, response to therapy, and tolerability of the regimen.
Because the autoinjector is designed to deliver the full content, the autoinjector should only be used for patients who need the full dose. If the required dose is not available in an autoinjector, pre-filled syringes or vials should be used to administer the required dose.
Recommended Dose and Dosage Adjustments
Recommended Dose
Chronic Hepatitis C Mono-infection
Table 4a PEGASYS RBV (peginterferon alfa-2a and ribavirin)
Dosing Recommendations
| Genotype | PEGASYS Dose | COPEGUS Dose (Take with food) | Duration |
| Genotype 1, 4 | 180 mcg | < 75 kg = 1000 mg ≥ 75 kg = 1200 mg | 48 weeks 48 weeks |
| Genotype 2, 3 | 180 mcg | 800 mg (regardless of weight) | 24 weeks |
PEGASYS (peginterferon alfa-2a)
The recommended dose of PEGASYS is 180 mcg administered subcutaneously in the abdomen or thigh once-weekly for 48 weeks for Genotype 1, 4 patients and for 24 weeks for Genotype 2, 3 patients.
The recommended duration of PEGASYS RBV treatment for patients previously untreated with interferon alfa-2a is 24 to 48 weeks. The duration of treatment should be individualized to the patient depending on baseline disease characteristics, response to therapy, and tolerability of the regimen.
A treatment duration of 24 weeks is recommended for Genotype 2, 3 patients and a treatment duration of 48 weeks is recommended for Genotype 1, 4 patients.
COPEGUS (ribavirin)
The daily dose of COPEGUS is 1000 mg to 1200 mg for 48 weeks for Genotype 1, 4 patients and 800 mg for 24 weeks for Genotype 2, 3 patients administered orally in two divided doses. The dose should be individualized to the patient depending on baseline disease characteristics (eg, genotype as indicated), response to therapy, and tolerability of the regimen (see Table 4a). In the pivotal clinical trials, patients were instructed to take COPEGUS with food; therefore, patients are advised to take COPEGUS with food.
HIV-HCV Co-infection
Table 4b PEGASYS RBV Dosing Recommendations
| Genotype | PEGASYS Dose | COPEGUS Dose (Take with food) | Duration |
| Genotype 1, 2, 3, 4 | 180 mcg | 800 mg (regardless of weight) | 48 weeks |
The recommended dosage of PEGASYS in combination with 800 mg daily COPEGUS (ribavirin) is 180 mcg once weekly subcutaneously for 48 weeks, regardless of genotype. The safety and efficacy of combination therapy with COPEGUS doses greater than 800 mg daily or a duration of therapy less than 48 weeks has not been studied.
Early Predictability of Response
After 12 weeks of treatment, virologic response should be assessed. Treatment discontinuation should be considered in any HCV (including HIV-HCV) patient who has not achieved viral clearance or an HCV-RNA reduction from baseline of at least 99% by week 12 (see CLINICAL TRIALS).
Dose Adjustments
PEGASYS:
General: When dose modification is required for moderate to severe adverse reactions (clinical and/or laboratory), initial dose reduction to 135 mcg is generally adequate. However, in some cases, dose reduction to 90 mcg is necessary. Following improvement of the adverse reaction, dose increases to or toward the original dose may be considered (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS).
Hematological: Dose reduction to 135 mcg PEGASYS is recommended if the ANC is less than 0.75 x 10⁹/L. For patients with ANC values below 0.5 x 10⁹/L, treatment should be suspended until ANC values return to over 1.0 x 10⁹/L. Therapy should initially be reinstituted at 90 mcg PEGASYS, and the ANC monitored.
Dose reduction to 90 mcg PEGASYS is recommended if the platelet count is less than
50 x 109/L. Cessation of therapy is recommended when platelet count decreases to levels below 25 x 109/L.
COPEGUS:
Table 5 COPEGUS Dosage Modification Guidelines for Management of Treatment
Emergent Anemia
| Laboratory Values | Reduce COPEGUS dose to 600 mg/day* only if: | Discontinue COPEGUS if**: |
| Hemoglobin: Patients with no cardiac disease | < 100 g/L | < 85 g/L |
| Hemoglobin: Patients with History of Stable cardiac disease | > 20 g/L decrease in hemoglobin during any 4 week period during treatment (permanent dose reduction) | < 120 g/L after 4 weeks of dose reduction |
* Patients whose dose of COPEGUS is reduced to 600 mg daily receive one 200 mg tablet in the morning and two 200 mg tablets in the evening.
** If the abnormality is reversed, COPEGUS may be restarted at 600 mg daily, and further increased to 800 mg daily at the discretion of the treating physician. However, a return to higher doses is not recommended.
In case of intolerance to COPEGUS, PEGASYS monotherapy may be continued.
Liver Function:
PEGASYS: Fluctuations in abnormalities of liver function tests are common in patients with chronic hepatitis. However, as with other alpha interferons, increases in ALT levels above baseline have been observed in patients treated with PEGASYS, including patients with a virological response.
The dose should be reduced initially to 90 mcg in the presence of progressive ALT increases above baseline values. When increase in ALT levels is progressive despite dose reduction, or is accompanied by increased bilirubin or evidence of hepatic decompensation, therapy should be discontinued.
Depression:
PEGASYS RBV should be used with extreme caution in patients who report a history of depression and physicians should monitor all patients for evidence of depression. For mild depression, no dose adjustment is necessary. For moderate depression, an initial dose reduction to 135 mcg is recommended; however, dose reduction to 90 mcg may be needed. Patients should be closely monitored. The frequency and nature of the monitoring should be based on the clinical judgment of the physician. If severe symptoms persist, therapy should be stopped and psychiatric intervention sought (see WARNINGS AND PRECAUTIONS).
Special Populations
Geriatric Use:
PEGASYS: No special dosage modification is required for geriatric patients with normal renal function, based upon pharmacokinetic, pharmacodynamic, tolerability, and safety data from clinical trials.
COPEGUS: There does not appear to be a significant age-related effect on the pharmacokinetics of ribavirin. However, as in younger patients, renal function must be determined prior to administration of COPEGUS.
Hepatic Impairment:
PEGASYS RBV has been shown to be effective and safe in patients with compensated cirrhosis (e.g. Child-Pugh A). PEGASYS RBV has not been studied in patients with decompensated liver disease (e.g. Child-Pugh B/C or bleeding esophageal varices) (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
The Child-Pugh classification divides patients into groups A, B, and C, or "Mild", "Moderate" and "Severe" corresponding to scores of 5-6, 7-9 and 10-15, respectively.
Table 6 Modified Assessment
| Assessment | Degree of abnormality | Score |
|---|---|---|
| Encephalopathy | None Grade 1-2 Grade 3-4* | 1 2 3 |
| Ascites | Absent Slight Moderate | 1 2 3 |
S-Bilirubin (mg/dL) SI unit = μmol/l) | <2 2-3 >3 <34 34-51 >51 | 1 2 3 1 2 3 |
| S-Albumin (g/L) | >35 35-28 <28 | 1 2 3 |
| INR | <1.7 1.7-2.3 >2.3 | 1 2 3 |
Grading according to Trey, Burns and Saunders (1966)
COPEGUS: No pharmacokinetic interaction appears between ribavirin and hepatic function. Therefore, no dose adjustment of COPEGUS is required in patients with hepatic impairment.
Renal Impairment:
PEGASYS: No dose adjustments in the recommended starting dose of PEGASYS 180 mcg once weekly is required in patients with creatinine clearance > 0.33 mL/sec. In patients with impaired renal function, signs and symptoms of interferon toxicity should be closely monitored.
In subjects with end-stage renal disease requiring hemodialysis, a starting dose of 135 mcg should be used. Regardless of the starting dose or degree of renal impairment, patients should be monitored and appropriate dose reductions of PEGASYS during the course of therapy should be made in the event of adverse reactions.
COPEGUS: The pharmacokinetics of ribavirin are altered in patients with renal dysfunction due to reduction of apparent clearance in these patients. Therefore, it is recommended that renal function be evaluated in all patients prior to initiation of COPEGUS, preferably by estimating the patient’s creatinine clearance. Substantial increases in ribavirin plasma concentrations are seen at the recommended dosing regimen in patients with serum creatinine > 177 µmol/L or with creatinine clearance < 0.83 mL/sec. There are insufficient data on the safety and efficacy in these patients and therefore, drug discontinuation, must be considered if adverse events develop (see WARNINGS AND PRECAUTIONS and ACTION AND PHARMACOLOGY: Pharmacokinetics of PEGASYS RBV in Special Populations).
Missed Dose
PEGASYS: If the PEGASYS dose is missed and remembered within 2 days of the scheduled dose, the PEGASYS dose should be administered as soon as possible. The next scheduled PEGASYS dose should be given on the usual day. If more than 2 days have elapsed, the dosage schedule should be based on the clinical judgement of the physician.
COPEGUS: If a COPEGUS dose is missed but remembered within the same day, it should be taken as soon as possible. If an entire day has passed, the next dose should be taken based on the clinical judgement of the physician. Two doses should not be taken at the same time.
Administration
PEGASYS is administered subcutaneously in the abdomen or thigh once-weekly (see DOSAGE AND ADMINISTRATION, Recommended Dose). Visually inspect the solution prior to administration. Do not use if discoloured or if particles are present.
COPEGUS is administered orally in two divided doses. In the pivotal clinical trials, patients were instructed to take COPEGUS with food; therefore, patients are advised to take COPEGUS with food (see DOSAGE AND ADMINISTRATION, Recommended Dose).
OVERDOSAGE
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
There is limited experience with overdosage with PEGASYS (peginterferon alfa-2a). The maximum dose received by any patient was 7 times the intended dose of PEGASYS (180 mcg/day for 7 days). There were no serious reactions attributed to overdosages. Weekly doses of up to 630 mcg have been administered to patients with cancer. Dose-limiting toxicities were fatigue, elevated liver enzymes, neutropenia and thrombocytopenia. There is no specific antidote for PEGASYS. Hemodialysis and peritoneal dialysis are not effective.
No cases of overdose with COPEGUS (ribavirin) have been reported in clinical trials. Absorption of ribavirin is generally complete after one hour. Hypocalcemia and hypomagnesemia have been observed in persons administered dosages greater than four times the maximal recommended dosages. In many of these cases ribavirin was administered intravenously. Treatment of overdose with ribavirin should consist of general supportive measures including monitoring of vital signs and observation of clinical status of the patient. There is no specific antidote for overdose with ribavirin. Ribavirin concentration is essentially unchanged by hemodialysis.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
Mechanism of Action
PEGASYS: Peginterferon alfa-2a possesses the in vitro antiviral and antiproliferative activities of interferon alfa-2a. Interferons bind to specific receptors on the cell surface initiating a complex intracellular signalling pathway and rapid activation of gene transcription. Interferon-stimulated genes modulate many biological effects including the inhibition of viral replication in infected cells, inhibition of cell proliferation, and immunomodulation. The clinical relevance of these in vitro activities is not known.
COPEGUS: The mechanism by which ribavirin in combination with peginterferon alfa-2a exerts its effects against hepatitis C virus (HCV) is unknown, although it is likely to involve both direct antiviral and immunomodulatory activities. More than additive inhibition of HCV subgenomic RNA replication in human liver cells has been seen in combination with PEGASYS.
Pharmacodynamics of PEGASYS
HCV RNA levels decline in a biphasic manner in responding patients with hepatitis C with and without compensated cirrhosis who have received treatment with 180 mcg PEGASYS. The first phase of decline occurs within 24 to 36 hours after the first dose of PEGASYS and the second phase of decline occurs over the next 4 to 16 weeks in patients who achieve a sustained response. Treatment with 180 mcg PEGASYS per week enhances the virion clearance and improves the virological end of treatment responses compared to treatment with interferon alfa-2a.
PEGASYS stimulates the production of effector proteins such as serum neopterin and 2', 5'-oligoadenylate synthetase (2', 5'-OAS) raises body temperature and causes reversible decreases in leukocyte and platelet counts. The stimulation of 2', 5'- OAS is maximal after single doses of 135 to 180 mcg PEGASYS and stays maximal throughout the one week dosing interval. The magnitude and duration of 2',5'-OAS activity induced by PEGASYS were reduced in subjects older than 62 years and in subjects with significant renal impairment (creatinine clearances of 0.33 to 0.67 mL/sec) compared to that seen in healthy subjects. The correlation between the in vitro and in vivo pharmacology and pharmacodynamic and clinical effects is unknown.
Pharmacokinetics
PEGASYS: The structure of the PEG moiety directly affects the clinical pharmacology of PEGASYS. Specifically, the size, branching and location of attachment of the 40 kD PEG moiety contribute to defining the absorption, distribution and elimination characteristics of PEGASYS. The pharmacokinetics of PEGASYS were studied in healthy volunteers and hepatitis C virus (HCV)-infected patients.
Absorption: The absorption of PEGASYS is sustained with peak serum concentrations reached 72 to 96 hours after dosing. Serum concentrations are measurable within 3 to 6 hours of a single dose. Dose proportional increases in AUC and Cmax are seen in patients that received once weekly doses of PEGASYS.
The absolute bioavailability of PEGASYS following sc administration in the abdomen is 84% and is similar to that seen with interferon alfa-2a.
Distribution: The volume of distribution at steady-state (Vss) of 6 to 14 liters after intravenous dosing suggests that the drug is found mainly in the bloodstream and extracellular fluid.
Metabolism: The metabolic profile of PEGASYS is not fully characterized.
Excretion: The systemic clearance of PEGASYS is about 100 mL/h, which is 100-fold lower than that of interferon alfa-2a. After an intravenous dose, the terminal half-life of PEGASYS in healthy subjects is about 60 hours compared to 3 to 4 hours for standard interferon. The terminal half-life after subcutaneous administration in patients is longer with a mean value of 160 hours (84 to 353 hours). The terminal half-life after subcutaneous dosing may be reflecting the sustained absorption of PEGASYS and not the elimination of the drug.
The kidneys eliminate less than 10% of a dose as the intact peginterferon alfa-2a. The rest is broken down metabolically.
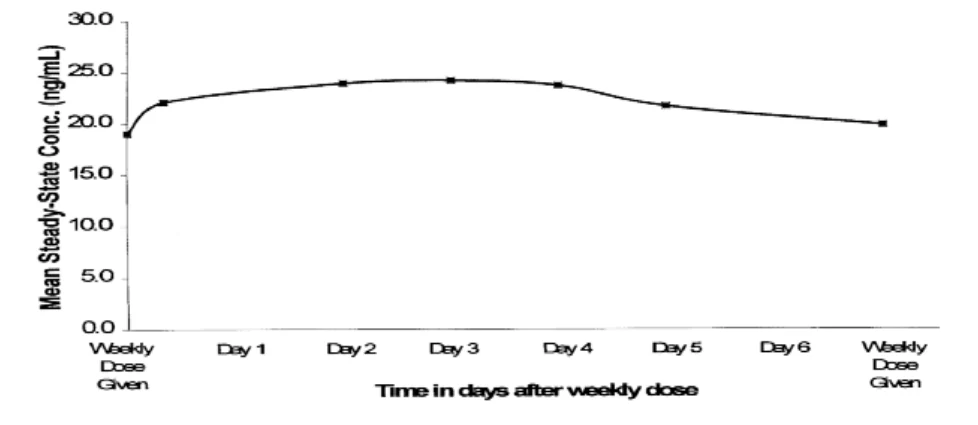
Steady state serum levels are reached within 5 to 8 weeks of once-weekly dosing. Once steady state has been achieved, there is no accumulation of peginterferon alfa-2a. The peak to trough ratio after 48 weeks of treatment is about 1.5 to 2.0. Peginterferon alfa-2a serum concentrations are sustained throughout the 1 week dosing interval (168 hours) [Table 7 and Figure 1].
Table 7 Pharmacokinetic Parameters of PEGASYS after single and multiple dose of 180 mcg
PEGASYS Pharmacokinetic Parameter | Healthy Subjects 180 mcg sc (N=50) | CHC Patients 180 mcg sc (N=16) | |
Single Dose Mean±SD [Range] | Single Dose Mean±SD [Range] | Week 48 Dose Mean±SD [Range] | |
| Cmax (ng/mL) | 14±5 [6-26] | 15±4 [7-23] | 26±9 [10-40] |
| Tmax (h) | 92±27 [48-168] | 80±28 [23-119] | 45±36 [0-97] |
| AUC1-168h (ng∙h/mL) | 1725±586 [524-3013] | 1820±586 [846-2609] | 3334±994 [1265-4824] |
| Clearance/F (mL/h) | 94±56 [34-337] | 83±50 [33-186] | 60±25 [37-142] |
| Week 48 trough concentration (ng/mL) | Not applicable | Not applicable | 16±6 [4-28] |
| Peak to trough ratio for week 48 | Not applicable | Not applicable | 1.7±0.4 [1.1-2.5] |
Accumulation (AUCWeek 48/AUCSingle Dose) | Not applicable | Not applicable | 2.3±1.0 [1.1-4.0] |
Figure 1 Mean steady-state PEGASYS concentrations in patients with CHC following
180 mcg peginterferon alfa-2a in combination therapy
COPEGUS:
Absorption: Orally administrated ribavirin is absorbed rapidly, reaching maximal plasma concentrations between 1 and 2 hours. The AUC0-192h and Cmax following a single oral dose of 600-mg of ribavirin ranged from 14 to 20 mg∙h/mL and from 650 to 770 ng/mL, respectively. Intersubject variability was high, with values of approximately 30% for AUC0-192h and 40% for Cmax. Absorption is extensive with about 10% to 15% of a radiolabelled dose excreted in the feces. However, the absolute bioavailability is between 33% to 65%, probably due to high first-pass metabolism. Ribavirin is absorbed from the gastrointestinal tract via an active sodium dependent nucleoside transport process. Since this process is saturable, less than proportional increases in Cmax were observed for doses above 800 mg. However, the exposure as measured by AUC0-192h was proportional up to a 2400-mg dose.
Bioavailability of a single oral dose of ribavirin was increased by co-administration with a high-fat meal. The absorption was slowed (Tmax was doubled) and the AUC0-192h and Cmax increased by 42% and 66%, respectively, when the ribavirin film-coated tablet was taken with a high-fat meal compared with fasting conditions.
Distribution: Ribavirin partitions into all cells rapidly and extensively and a very large steady-state volume of distribution of about 850 liters after intravenous dosing. This distribution is facilitated by the sodium independent es nucleoside transporter that is present in all types of cells and thus ribavirin accumulates in erythrocytes, ova and spermatozoa. Ribavirin sequesters in erythrocytes extensively with a ratio of 60:1 between whole blood and plasma concentrations. Ribavirin does not bind to plasma proteins.
Metabolism: Ribavirin is metabolized via two major pathways:
- A reversible phosphorylation in nucleated cells forming mono-, di-, and tri-phosphate metabolites and
Deribosylation and amide hydrolysis forming the triazole carboxylic acid metabolite. The triazole carboxylic acid and triazole carboxamide were the principal metabolites. The
- cytochrome P450 enzyme system is not involved in the metabolism of ribavirin.
Excretion: Both renal excretion and metabolism are major routes of elimination of ribavirin in humans and animals. Total body clearance after intravenous dosing was about 20 L/h to 25 L/h, with about 30% accounted for by renal clearance. In humans, about 61% of the radioactivity of a 600-mg oral dose was eliminated in the urine within 336 hours, of which unchanged ribavirin accounted for 17%.
Due to extensive distribution, the terminal half-life of a single oral or intravenous dose is about 120 to 170 hours. This half-life is further prolonged to 270 to 300 hours following multiple doses. Extensive accumulation of ribavirin is seen after multiple dosing (BID) such that the AUC at steady state was sixfold higher than that of a single dose.
Pharmacokinetics Analysis of PEGASYS RBV
No pharmacokinetic interactions between PEGASYS and COPEGUS have been observed in clinical trials in which PEGASYS is used in combination with COPEGUS. Results from a pharmacokinetic substudy of a pivotal phase III trial demonstrated no pharmacokinetic interaction between peginterferon alfa-2a and ribavirin.
Special Populations and Conditions
Pediatrics (<18 years of age):
PEGASYS: The pharmacokinetics of PEGASYS have not been adequately studied in pediatric patients.
COPEGUS: Pharmacokinetic evaluations in pediatric patients have not been performed.
Geriatrics:
PEGASYS: In subjects older than 62 years, the AUC was modestly increased (1663 vs 1295 ng∙h/mL, older than 62 years vs younger, respectively), but peak concentrations (9.1 vs 10.3 ng/mL) were similar in the two age groups (see DOSAGE AND ADMINISTRATION).
COPEGUS: Specific pharmacokinetic evaluations for elderly patients have not been performed. However, in a published population pharmacokinetic study, age was not a key factor in the kinetics of ribavirin; renal function is the determining factor.
Gender:
PEGASYS: The pharmacokinetics of PEGASYS after single subcutaneous injections were comparable between male and female healthy subjects.
COPEGUS: No clinically significant differences in the pharmacokinetics of ribavirin were observed between male and female subjects in a population pharmacokinetic analysis of 3600 sparsely collected serum concentration data from 138 patients.
Race:
PEGASYS: In a pharmacokinetic study in 40 CHC patients, no ethnicity-based differences in PEGASYS pharmacokinetic parameters were observed between Black (n=13) and Caucasian
(n=15) patients or Hispanic (n=12) and Caucasian patients.
COPEGUS: A pharmacokinetic study in 42 CHC patients demonstrated there is no clinically significant difference in ribavirin pharmacokinetics among Black (n=14), Hispanic (n=13) and Caucasian (n=15) patients.
Hepatic Insufficency:
PEGASYS: The pharmacokinetics of PEGASYS were similar between healthy subjects and patients with hepatitis C. Comparable pharmacokinetic profiles were seen in cirrhotic patients with compensated liver disease and patients without cirrhosis.
COPEGUS: Single-dose pharmacokinetics of ribavirin in patients with mild, moderate or severe hepatic dysfunction are similar to those of normal controls.
Renal Insufficency:
PEGASYS: Renal impairment is associated with decreased total apparent clearance and prolonged half-life. In subjects with a creatinine clearance between 0.33 and 0.67 mL/sec, the average total apparent clearance is reduced by approximately 30% compared with subjects with normal renal function following single doses of PEGASYS. Adverse events and laboratory abnormalities that occurred during the study were those expected following interferon administration and occurred with only slightly greater frequency in subjects with renal impairment (see WARNINGS AND PRECAUTIONS).
In subjects with end-stage renal disease undergoing hemodialysis, there is a 25% to 45% reduction in the clearance of peginterferon alfa-2a and doses of 135 mcg provide exposure similar to those observed in subjects with normal renal function receiving 180 mcg doses. Regardless of the starting dose or degree of renal impairment, patients should be monitored and appropriate dose reductions of PEGASYS during the course of therapy should be made in the event of adverse reactions (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION: Dose Adjustments).
COPEGUS: Single-dose ribavirin pharmacokinetics were altered (increased AUCtf and Cmax) in patients with renal dysfunction compared with control subjects whose creatinine clearance was greater than 1.50 mL/sec. The oral clearance of ribavirin is substantially reduced in patients with serum creatinine > 177 µmol/L or creatinine clearance < 0.83 mL/sec. There are insufficient data on the safety and efficacy of ribavirin in these patients and therefore, COPEGUS must be administered with extreme caution and corrective action including drug discontinuation must be considered if adverse events develop (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION: Dose Adjustments). Plasma concentrations of ribavirin are essentially unchanged by hemodialysis.
Genetic Polymorphism: Different HCV genotypes display considerable clinical variability in their response to PEGASYS and COPEGUS. Viral genetic determinants associated with the variable response have not been definitively identified.
STORAGE AND STABILITY
Stability and Storage Recommendations:
Store PEGASYS RBV (peginterferon alfa-2a and ribavirin) packages in the refrigerator at 2-8°C. Protect from light. Do not freeze or shake. Do not use PEGASYS RBV beyond the date of expiry.
If package components are separated: Store PEGASYS vials, autoinjectors or pre-filled syringes in the refrigerator at 2-8°C. Protect from light. Do not freeze or shake. Do not use PEGASYS beyond the date of expiry.
Parenteral drug products such as PEGASYS should be inspected visually for particulate matter and discolouration before administration. Do not use PEGASYS if it contains particulate matter or it appears discoloured. Store COPEGUS below 30°C or under refrigeration. Keep bottle tightly closed.
SPECIAL HANDLING INSTRUCTIONS
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
Disposal of syringes/sharps:
The following points should be strictly adhered to regarding the use and disposal of syringes and other medicinal sharps:
- Needles and syringes should never be reused.
- Place all used needles, autoinjectors and syringes into a sharps container (puncture-proof disposable container).
- Keep this container out of the reach of children.
- Placing used sharps containers in the household waste should be avoided.
- Dispose of the full container according to local requirements or as instructed by your healthcare provider
For home use, a puncture resistant container for the disposal of used syringes, autoinjectors and needles should be supplied to the patients.
Disposal of unused/expired medicines:
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided. Use established “collection systems” if available in your location.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage forms:
PEGASYS (peginterferon alfa-2a) is a sterile, ready-to-use solution for subcutaneous injection. PEGASYS is supplied as 180 mcg/0.5 mL in single-use, graduated, clear glass pre-filled syringes and as 180 mcg/mL in single-use, clear glass vials. PEGASYS ProClick™ is supplied as 180 mcg/0.5 mL in single-use, disposable autoinjectors.
COPEGUS (ribavirin) is a light pink to pink, flat, oval, film-coated tablet with RIB and 200 engraved on one side and ROCHE on the other side. Each tablet contains 200 mg ribavirin for oral administration.
Composition:
PEGASYS Pre-filled Syringe: Each 0.5 mL contains 180 mcg of peginterferon alfa-2a (expressed as the amount of interferon alfa-2a), 4.0 mg sodium chloride, 0.025 mg polysorbate 80, 5.0 mg benzyl alcohol, 1.3085 mg sodium acetate trihydrate, 0.0231 mg acetic acid and water for injection, at pH 6 ± 0.2.
PEGASYS Vial: Each 1 mL vial contains 180 mcg of peginterferon alfa-2a (expressed as the amount of interferon alfa-2a), 8.0 mg sodium chloride, 0.05 mg polysorbate 80, 10.0 mg benzyl alcohol, 2.617 mg sodium acetate trihydrate, 0.0462 mg acetic acid and water for injection, at pH 6 ± 0.2.
PEGASYS ProClick® Autoinjector: Each 0.5 mL contains 180 mcg of peginterferon alfa-2a (expressed as the amount of interferon alfa-2a), 4.0 mg sodium chloride, 0.025 mg polysorbate 80, 5.0 mg benzyl alcohol, 1.3085 mg sodium acetate trihydrate, 0.0231 mg acetic acid and water for injection, at pH 6 ± 0.2.
The ready to use autoinjector includes a post-injection needle shield that was designed to help prevent needle-stick injuries and keeps the needle non-visible.
COPEGUS Tablets: Each COPEGUS tablet contains 200 mg ribavirin. Non-medicinal ingredients are: pregelatinized starch, sodium starch glycolate, microcrystalline cellulose, maize starch, magnesium stearate, ethyl cellulose, hydroxypropyl methylcellulose, titanium dioxide, talc, iron oxide yellow, iron oxide red, and triacetin.
Packaging:
PEGASYS RBV (peginterferon alfa-2a and ribavirin) is available in the following packaging configurations that provide sufficient peginterferon alfa-2a and ribavirin for 1 and 4 weeks of therapy:
PEGASYS RBV - PEGASYS Pre-filled syringes (PFS) and COPEGUS
| 1 carton containing | 1 PFS of PEGASYS 180 mcg/0.5 mL and 1 injection needle* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 28 tablets | |
| 1 carton containing | 1 PFS of PEGASYS 180 mcg/0.5 mL and 1 injection needle* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 35 tablets |
| 1 carton containing | 1 PFS of PEGASYS 180 mcg/0.5 mL and 1 injection needle* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 42 tablets | |
| 1 carton containing | 4 PFS of PEGASYS 180 mcg/0.5 mL and 4 injection needles* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 112 tablets | |
| 1 carton containing | 4 PFS of PEGASYS 180 mcg/0.5 mL and 4 injection needles* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 140 tablets | |
| 1 carton containing | 4 PFS of PEGASYS 180 mcg/0.5 mL and 4 injection needles* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 168 tablets | |
| 1 carton containing | 4 PFS of PEGASYS 180 mcg/0.5 mL and 4 injection needles* (27 gauge x ½ inch) |
| 1 bottle of COPEGUS containing 168 tablets + 1 bottle of COPEGUS containing 28 tablets |
* Injection needle manufactured by Terumo Europe N. V., Interleuvenlaan 40 Leuven, ZZ, Belgium 3001
PEGASYS RBV - PEGASYS vials and COPEGUS
| 1 carton containing | 1 vial of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 28 tablets | |
| 1 carton containing | 1 vial of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 35 tablets | |
| 1 carton containing | 1 vial of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 42 tablets | |
| 1 carton containing | 4 vials of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 112 tablets | |
| 1 carton containing | 4 vials of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 140 tablets | |
| 1 carton containing | 4 vials of PEGASYS 180 mcg/mL |
| 1 bottle of COPEGUS containing 168 tablets |
PEGASYS RBV - PEGASYS ProClick® Autoinjector and COPEGUS
| 1 carton containing | 1 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 28 tablets | |
| 1 carton containing | 1 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 35 tablets | |
| 1 carton containing | 1 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 42 tablets | |
| 1 carton containing | 4 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 112 tablets | |
| 1 carton containing | 4 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 140 tablets | |
| 1 carton containing | 4 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 168 tablets | |
| 1 carton containing | 4 PEGASYS ProClick® Autoinjector 180 mcg/0.5 mL |
| 1 bottle of COPEGUS containing 168 tablets + 1 bottle of COPEGUS containing 28 tablets |
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper Name | Peginterferon alfa-2a (INN) | Ribavirin |
| Chemical Name | Bis-(N-monomethoxypolyethyleneglycol-urethanyl) lysyl interferon alfa-2a. | 1-β-D-Ribofuranosyl-1H- 1,2,4-triazole-3-carboxamide |
| Molecular formula and molecular mass | Peginterferon alfa-2a is made by conjugating a single branched polyethylene glycol chain (PEG), of approximate molecular weight of 40,000 dalton, to interferon alfa-2a (20,000 dalton) via a stable amide bond. Interferon alfa-2a is a monomeric protein containing 165 amino acids with a molecular formula C860H1349N227O255S9. | 244.2 C8H12N4O5 |
| Structural Formula | 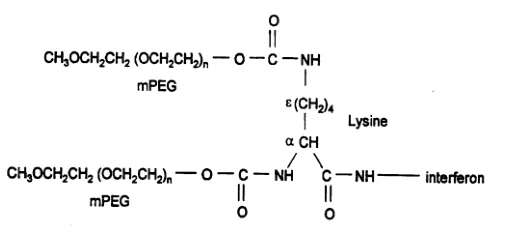 | N N N C O N H 2 O H O C H 2 H O O H |
| Physicochemical properties: | Colourless to light yellow solution | White to off-white powder |
| Other Properties | _ | Ribavirin is freely soluble in water and exhibits lower solubility in organic solvents. The pKa of ribavirin is 12.25; the pH of a 2.0% w/v aqueous solution of ribavirin is approximately 6.3. Ribavirin melts between 166-168°C. The partition coefficient (1-octanol/water): log P=-2.24. |
CLINICAL TRIALS
For information on clinical studies with PEGASYS RBV (peginterferon alfa-2a and ribavirin) in combination with other HCV antiviral drugs authorized for use in Canada, refer to their Product Monographs.
Chronic Hepatitis C Mono-infection
The safety and effectiveness of PEGASYS RBV (peginterferon alfa-2a and ribavirin) for the treatment of hepatitis C virus infection were assessed in two randomized controlled clinical trials. All patients were adults, had compensated liver disease, detectable hepatitis C virus, liver biopsy diagnosis of chronic hepatitis, elevated serum ALT activity and were previously untreated with interferon. Approximately 20% of patients in both studies had compensated cirrhosis.
Table 8 Summary of patient demographics for clinical trials for the treatment of
Chronic Hepatitis C mono-infection
| Study # | Trial Design | Dosage, route of administration and duration | Number | Gender | Mean age (Range) | % HCV Genotype 1 | ||
|---|---|---|---|---|---|---|---|---|
| Study 1 | Randomized, multicentre, partially blinded, active-controlled and placebo-controlled study. | PEGASYS 180 mcg sc once weekly with placebo, oral for 48 weeks of therapy followed by 24 weeks of treatment-free follow-up. | 224 | Male/Female (151/73) | 42.4 years (19 – 64) | 65% | ||
| PEGASYS 180 mcg sc once weekly with COPEGUS 1000 mg, oral (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) for 48 weeks of therapy followed by 24 weeks of treatment-free follow-up. | 453 | Male/Female (324/129) | 42.8 years (19 – 76) | 66% | ||||
| Interferon alfa-2b plus ribavirin (active control), oral for 48 weeks of therapy followed by 24 weeks of treatment-free follow-up. | 444 | Male/Female (325/119) | 42.3 years (20 – 71) | 64% | ||||
| Study 2 | Randomized, multicentre, double blind study | PEGASYS 180 mcg sc qw with COPEGUS 800 mg for 24 weeks, followed by 24 weeks of treatment-free follow-up. | 207 | Male/Female (140/67) | 41.2 years (18 – 66) | 49% | ||
| PEGASYS 180 mcg sc qw with COPEGUS 1000 mg (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) for 24 weeks, followed by 24 weeks of treatment-free follow-up. | 280 | Male/Female (185/95) | 42.0 years (19 – 76) | 42% | ||||
| PEGASYS 180 mcg sc qw with COPEGUS 800 mg for 48 weeks followed by 24 weeks of treatment-free follow-up. | 361 | Male/Female (226/135) | 42.6 years (19 – 74) | 69% | ||||
| PEGASYS 180 mcg sc qw with COPEGUS 1000 mg (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) for 48 weeks followed by 24 weeks of treatment-free follow-up. | 436 | Male/Female (287/149) | 43.0 years (20 – 73) | 62% | ||||
Study 1
Study 1 was a randomized, multicentre, partially blinded, active-controlled and placebo-controlled study that was designed to demonstrate the superiority (efficacy and safety) of PEGASYS RBV (a pegylated interferon plus ribavirin) combination therapy over interferon alfa-2b (a non-pegylated interferon) and ribavirin and PEGASYS monotherapy. Patients were randomized to receive either PEGASYS 180 mcg sc once weekly (qw) with placebo, PEGASYS 180 mcg sc qw with COPEGUS 1000 mg (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) or interferon alfa-2b plus ribavirin (active control) for 48 weeks of therapy followed by 24 weeks of treatment-free follow-up. COPEGUS or placebo treatment assignment was blinded. The study enrolled 1149 patients of which 28 never received treatment; the 1121 patients receiving treatment were 71% male, 84% Caucasian, 13% with cirrhosis or developing cirrhosis, and 65% genotype 1.
The sustained virological response (SVR) to treatment presented in Table 9, is defined as an undetectable HCV RNA (COBAS AMPLICOR™ HCV Test, version 2.0) value at the end of the treatment-free follow-up period in patients who received at least one dose of study medication.
The SVR of PEGASYS RBV combination therapy for 48 weeks was statistically significantly higher than the SVR of interferon alfa-2b and ribavirin (overall and by genotype). The SVR for patients with cirrhosis or developing cirrhosis treated with PEGASYS 180 mcg and COPEGUS 1000 mg or 1200 mg for 48 weeks was 41 % (n=23/56) (compared to 33% (n=18/54) for interferon alfa-2b 3 MIU and ribavirin 1000 - 1200 mg). Improvement over interferon alfa-2b and ribavirin was seen in patients with either high or low viral load (see Table 9). The SVR of the PEGASYS 180 mcg arm was essentially the same as that seen in clinical studies evaluating monotherapy.
Table 9 Response to Treatment
| Study 1 | ||||||||||||||
Interferon alfa-2b + ribavirin (I + R) 1000 mg or 1200 mg 48 Weeks | PEGASYS + Placebo (P) 48 Weeks | PEGASYS + COPEGUS (P + C) 1000 mg or 1200 mg 48 Weeks | ||||||||||||
| N | SVR | N | SVR | N | SVR | |||||||||
Sustained Virological Response All patients a | 444 | 198 (45%) | 224 | 65 (29%) | 453 | 245 (54%) | ||||||||
| Genotype 1 Patients b | 285 | 103 (36%) | 145 | 29 (20%) | 298 | 134 (45%) | ||||||||
| Low viral load1 | 94 | 41 (44%) | 44 | 16 (36%) | 115 | 61 (53%) | ||||||||
| High viral load2 | 189 | 62 (33%) | 101 | 13 (13%) | 182 | 73 (40%) | ||||||||
| Genotype non-1 Patients c | 159 | 95 (60%) | 79 | 36 (46%) | 155 | 111 (72%) | ||||||||
| Low viral load1 | 56 | 38 (68%) | 25 | 15 (60%) | 44 | 33 (75%) | ||||||||
| High viral load2 | 103 | 57 (55%) | 54 | 21 (39%) | 111 | 78 (70%) | ||||||||
a Cochran-Mantel-Haenszel test - P+C vs I + R (p= 0.003); P + C vs P (p=0.001); I + R vs P (p=0.001)
b Cochran-Mantel-Haenszel test - P+C vs I + R (p= 0.031); P + C vs P (p=0.001); I + R vs P (p=0.001)
c Cochran-Mantel-Haenszel test - P+C vs I + R (p= 0.036); P + C vs P (p=0.001); I + R vs P (p=0.001)
1Low viral load ≤ 800,000 IU/mL; 2High viral load > 800,000 IU/mL
An administrative amendment was made to the protocol for Study 1 to obtain follow-up data on 125 patients whose last HCV RNA PCR measurement was undetectable or indeterminate (i.e. detectable by the COBAS AMPLICOR™ HCV Test, version 2.0 but not by the COBAS AMPLICOR HCV Monitor™ Test, version 2.0) at week 60 or 72 and who did not have two (2) consecutive measurements at week 60 or later (including those who were lost to follow-up while responding virologically). Follow-up data were collected for 68 of the 125 patients. The last single HCV RNA measurement was undetectable on or after week 68 in 264/453 patients treated with PEGASYS RBV, SVR of 58 %. The corresponding SVRs for the interferon alfa and ribavirin and PEGASYS monotherapy treatment arms were 214/444 (48%) and 67/224 (30%), respectively.
Sustained biochemical response at week 72 was highest among patients receiving PEGASYS RBV (50%) and statistically superior to the sustained biochemical response observed with interferon alfa-2b and ribavirin (43%, p=0.02) and PEGASYS monotherapy (32%, p=0.001). The difference in biochemical response between the patients treated with interferon alfa-2b and ribavirin and patients who received PEGASYS monotherapy was also statistically significant (p=0.004).
Paired biopsies were obtained in a subset of patients (17%) to evaluate the histological benefit of PEGASYS therapy. At the end of follow-up, 80% of patients who had a paired biopsy and were treated with PEGASYS RBV combination therapy had a histological response versus 76% of patients treated with interferon alfa-2b and ribavirin and 72% of patients treated with PEGASYS monotherapy. Sustained virological response was associated with histological response in most patients. Among patients with a sustained virological response and paired biopsies, 89% (100 of 112 patients) had a histological response. Histological response was defined as ≥ 2 point decrease in total HAI score at end of follow-up as compared with pretreatment.
Published Literature
In the publication of Study 1, by Fried et al., the comparison between PEGASYS 180 mcg + COPEGUS (1000 mg or 1200 mg) and interferon alfa-2b 3 MIU and ribavirin (1000 mg or 1200 mg) was reported with the following SVRs. Overall SVR in patients treated for 48 weeks was 56% for PEGASYS + COPEGUS versus interferon alfa-2b 3 MIU + ribavirin (44%, p<0.001). Genotype 1 patients receiving PEGASYS + COPEGUS (46% vs 36%, p=0.01); Genotype 1 with low viral load (56% vs 43%, p=NA); Genotype 1 with high viral load (41% vs 33%, p=NA); Genotype 2 and 3 (achieved an SVR of 76% vs 61%, p=0.005); Genotype 2 or 3 with low viral load (81% vs 65%, p=NA) and Genotype 2 or 3 patients with high viral load (74% vs 58%, p=NA).
Study 2
Study 2 was a randomized, multicentre, double-blind study that was prospectively designed to evaluate the duration of PEGASYS RBV treatment (24 weeks vs 48 weeks of treatment) and COPEGUS dose (800 mg fixed dose vs 1000 or 1200 mg by body weight) in patients randomized by HCV genotype and viral load. Patients were randomized to receive either PEGASYS 180 mcg sc qw with COPEGUS 800 mg for 24 weeks, PEGASYS 180 mcg sc qw with COPEGUS 1000 mg (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) for 24 weeks, PEGASYS 180 mcg sc qw with COPEGUS 800 mg for 48 weeks or PEGASYS 180 mcg sc qw with COPEGUS 1000 mg (body weight <75 kg) or 1200 mg (body weight ≥ 75 kg) for 48 weeks followed by 24 weeks of treatment-free follow-up. The study enrolled 1311 patients of which 27 never received treatment; the 1284 treated patients were 65% male, 89% Caucasian, 25% with cirrhosis or developing cirrhosis, and genotype 1 varied by treatment group (42% to 69%).
The SVR to treatment presented in Table 10 is defined as an undetectable HCV RNA (COBAS AMPLICOR™ HCV Test, version 2.0) value at the end of the treatment-free follow-up period at or beyond week 44 (24 week treatment groups) or week 68 (48 week treatment groups).
Table 10 Rates of Response to Treatment Based on Genotype and Viral Load
| 24 Weeks Treatment | 48 Weeks Treatment | |||||||||||||||||
| PEGASYS + COPEGUS 800 mg | PEGASYS + COPEGUS 1000 mg or 1200 mg | PEGASYS + COPEGUS 800 mg | PEGASYS + COPEGUS 1000 mg or 1200 mg | |||||||||||||||
| N | SVR | N | SVR | N | SVR | N | SVR | |||||||||||
| All patients | 207 | n/a | 280 | n/a | 361 | n/a | 436 | 265 (61%) | ||||||||||
| Genotype 1 | 101 | 29 (29%) | 118 | 48 (41%) | 250 | 99 (40%) | 271 | 138 (51%) | ||||||||||
| Low viral load | 51 | 21 (41%) | 71 | 36 (51%) | 60 | 32 (53%) | 85 | 52 (61%) | ||||||||||
| High viral load | 50 | 8 (16%) | 47 | 12 (26%) | 190 | 67 (35%) | 186 | 86 (46%) | ||||||||||
| Genotype non-1 | 106 | 83 (78%) | 162 | 127 (78%) | 111 | 81 (73%) | 165 | 127 (77%) | ||||||||||
| Low viral load | 39 | 28 (72%) | 61 | 47 (77%) | 41 | 32 (78%) | 57 | 44 (77%) | ||||||||||
| High viral load | 67 | 55 (82%) | 101 | 80 (79%) | 70 | 49 (70%) | 108 | 83 (77%) | ||||||||||
The SVR in genotype 1 patients, irrespective of low or high viral load, was highest in the group treated for 48 weeks with 1000 mg or 1200 mg of COPEGUS in patients with and without cirrhosis. The SVR in genotype 1 cirrhosis or developing cirrhosis patients who were treated with PEGASYS 180 mcg and COPEGUS 1000 mg or 1200 mg for 48 weeks was 41% (n=32/78). The SVR for all patients treated with PEGASYS 180 mcg and COPEGUS 1000 mg or 1200 mg for 48 weeks was 61 % (n=265/436). The SVR for patients with cirrhosis or developing cirrhosis was 50 % (n=58/115).
The study results demonstrated that treatment for 24 weeks with PEGASYS RBV combination therapy in patients infected with genotype non-1 (predominantly genotypes 2 and 3), was as efficacious as treatment for 48 weeks in patients infected with genotype non-1, either with low or high viral load. In genotype non-1 genotypes 2 and 3 patients, the 800 mg dose of COPEGUS was as effective as the 1000 mg or 1200 mg dose of COPEGUS. In the small number of patients evaluated with genotype 4 across all treatment groups (n=36), the SVR was highest in the group of patients treated for 48 weeks with 1000 mg or 1200 mg of COPEGUS (n=9/11, 82%). The SVR (73%) in genotype 2 and 3 patients with cirrhosis or developing cirrhosis treated for 48 weeks with PEGASYS 180 mcg and 1000 mg or 1200 mg of COPEGUS was similar to the SVR (70%) for 24 weeks of treatment with PEGASYS 180 mcg and 800 mg of COPEGUS.
Paired biopsies were obtained in a subset of patients (20%). Percentages of patients with a histological response were similar in all four treatment groups and ranged from 72% to 78%. The total HAI score with fibrosis decreased in all four treatment groups, and the median change ranged from -3.5 to -4. There were nine patients whose HAI score worsened. None of these patients were sustained virological responders.
There was a good correlation between SVR and histological response; 79% to 97% of patients with a SVR also had a histological response across all treatment groups.
Published Literature
In publication of Study 2, by Hadziyannis et al., the overall SVR in patients treated for 48 weeks with PEGASYS 180 mcg and COPEGUS (1000 or 1200 mg) was 63%. In this arm, results were further reported as follows: Genotype 1 patients had an SVR of 52%, Genotype 1 with low viral load had an SVR of 65%, and those with high viral load had an SVR of 47%. In another arm of the study, Genotype 2 and 3 patients were treated for 24 weeks with PEGASYS 180 mcg and COPEGUS 800 mg. This arm reported SVRs in 84% of patients. Low viral load patients achieved an SVR of 85%, and high viral load achieved an SVR of 84%.
Predictability of Response
Patients who do not demonstrate an early virological response (defined as achieving undetectable levels of HCV RNA or at least a 99% reduction in viral titer from baseline by the end of 12 weeks of treatment) to PEGASYS RBV combination therapy are unlikely to achieve a SVR at week 72 with continuation of treatment. Among patients treated with PEGASYS 180 mcg and COPEGUS 1000 mg or 1200 mg combination therapy in the studies 1 and 2, 108 of the 113 patients with a lack of an early virological response did not achieve a SVR at week 72. The results of this analysis indicate a 96% negative predictability by week 12. For difficult to treat patients (genotype 1, high viral load) on PEGASYS RBV combination therapy, all patients without an early virological response did not achieve a SVR at week 72, indicating a 100% negative predictability by week 12. Consideration should be given to discontinuing therapy if virological results by week 12 do not indicate a response to therapy.
Among patients achieving an early virological response, the rate of sustained virological response was as high as 75% in those who maintained the full dosing schedule (at least 80% of the planned treatment).
Anti-Interferon Antibodies
A total of 14 out of 294 patients (4.8%) treated with 180 mcg PEGASYS and 1000-1200 mg COPEGUS developed neutralizing anti-interferon antibodies. The development of neutralizing anti-interferon antibodies does not preclude achieving a sustained virological response. Nine (9) of the 14 patients who developed neutralizing anti-interferon antibodies had a sustained virological response.
HIV-HCV Co-Infection
Study 3
In the co-infection clinical trial, study 3, 859 HIV-HCV co-infected patients were randomized and treated with PEGASYS, PEGASYS RBV or interferon alfa-2a 3 MIU three times weekly and ribavirin 800 mg/day for 48 weeks followed by a 24 week treatment free follow-up. The sustained virologic responses for the three treatment groups are summarized for all patients and by genotype in Table 12.
Table 11 Summary of patient demographics for clinical trials in HCV-HIV co-infection
| Study # | Trial Design | Dosage, route of administration and duration | Number | Gender | Mean age (Range) | % HCV Genotype 1 | |||||
| Study 3 | randomized, multicentre, partially blinded, active-controlled and placebo-controlled study and drug interaction nested trial between PEG-IFN alfa-2a and protease inhibitors. | PEGASYS 180 mcg/week and placebo for 8 weeks followed by a 24 week treatment free follow-up. | 286 | Male/Female (234/52) | 40.0 years (22 – 66) | 61% | |||||
| PEGASYS 180 mcg/week and COPEGUS 800 mg/day for 48 weeks followed by a 24 week treatment free follow-up. | 288 | Male/Femal e (232/57) | 39.7 years (20 – 64) | 61% | |||||||
| Interferon alfa-2a 3 MIU three times weekly and ribavirin 800 mg/day for 48 weeks followed by a 24 week treatment free follow-up. | 285 | Male/Femal e (231/54) | 40.1 years (18 – 74) | 60% | |||||||
Table 12 Sustained Virologic Response in HIV-HCV Co-infected Patients
PEGASYS 180mcg + Placebo 48 weeks | PEGASYS 180mcg + COPEGUS 800 mg 48 weeks | Interferon alfa-2a 3MIU + COPEGUS 800 mg 48 weeks | |
| All patients | 20% (58/286)* | 40% (116/289)* | 12% (33/285)* |
| Genotype 1 | 14% (24/175) | 29% (51/176) | 7% (12/171) |
| Genotype 2/3 | 36% (32/90) | 62% (59/95) | 20% (18/89) |
* PEGASYS 180mcg COPEGUS 800mg vs. Interferon alfa-2a 3MIU COPEGUS 800mg: Odds Ratio (95% CI ) = 5.40 (3.42 to 8.54)
p-value (stratified Cochran-Mantel-Haenszel test) = < 0.0001
* PEGASYS 180mcg COPEGUS 800mg vs. PEGASYS 180mcg: Odds Ratio (95% CI ): 2.89 (1.93 to 4.32), p-value (stratified Cochran-Mantel-Haenszel test) = < 0.0001
* Interferon alfa-2a 3 MIU COPEGUS 800 mg vs. PEGASYS 180mcg: Odds Ratio (95% CI ): 0.53 (0.33 to 0.85), p-value (stratified Cochran-Mantel-Haenszel test) = < 0.0084
Predictability of Response
Patients who do not demonstrate an early virological response (defined as achieving undetectable levels of HCV RNA or at least a 99% reduction in viral titer from baseline by the end of 12 weeks of treatment) to PEGASYS RBV combination therapy are unlikely to achieve a SVR at week 72 with continuation of treatment. In co-infection clinical study 3, the negative predictive value that has been observed in HIV-HCV co-infected patients treated with PEGASYS RBV was
(98%). Positive predictive value of 45% and 70% were observed for genotype 1 and genotype 2/3 HIV-HCV co-infected patients receiving PEGASYS RBV combination therapy, respectively.
DETAILED PHARMACOLOGY
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
Nonclinical Pharmacology:
Peginterferon alfa-2a: The preclinical studies have demonstrated that peginterferon alfa-2a (PEG-IFN) retains the ability to bind to the alpha interferon receptor, to activate interferon-induced signaling pathways, and to stimulate the expression of a known interferon-inducible human gene in vitro. PEG-IFN has also been shown to retain antiviral and antiproliferative properties typical of an alpha interferon. These in vitro data support the hypothesis that the biological activity of interferon alfa-2a (IFN) is retained following the pegylation process and is mediated by the IFN portion of the PEG-IFN molecule, acting via a classical alpha interferon pathway.
The in vivo studies demonstrate that PEG-IFN retains biological activity as shown by induction of 2,5-OAS activity in the monkey and by reduction of tumor xenograft growth and regression in the mouse. The comparison of once weekly administration of PEG-IFN with three times weekly administration of IFN in the mouse model demonstrates that the in vivo biological activity of PEG-IFN is enhanced compared with IFN.
Safety pharmacology studies were conducted to evaluate the effects of PEG-IFN on the cardiovascular, respiratory, renal, gastrointestinal and central nervous systems. Decreases in urine volume accompanied by decreases in urinary potassium levels were noted after sc administration of PEG-IFN to saline-loaded rats. In cynomolgus monkeys a slight tachycardia was observed following iv administration of PEG-IFN.
Studies designed to investigate the apparent neutropenia observed in clinical studies following PEG-IFN administration, and to show the effect of administration of G-CSF (filgrastim) on neutrophil counts, were conducted in female mice. Due to the species specificity of IFN, a pegylated form of hybrid human IFN (PEG-IFNαA/D), which is active on murine cells was used.
Treatment of female mice with PEG-IFNαA/D resulted in lymphopenia in the peripheral blood and to a lesser extent in the bone marrow. In addition, neutropenia, reticulocytopenia and thrombocytopenia were observed in the peripheral blood. Treatment with filgrastim on days 2 and 3 ameliorated the neutropenia caused by a single dose of PEG-IFNαA/D.
Ribavirin: Ribavirin, a synthetic nucleoside analog, has shown in vitro activity against some RNA and DNA viruses, as well as immunomodulatory activity. The mechanism by which ribavirin in combination with peginterferon alfa-2a exerts its effects against hepatitis C virus (HCV) is unknown, although it is likely to involve both direct antiviral and immunomodulatory activities. More than additive inhibition of HCV subgenomic RNA replication in human liver cells has been seen in combination with PEGASYS (peginterferon alfa-2a).
TOXICOLOGY
PEGASYS RBV (peginterferon alfa-2a and ribavirin)
Peginterferon alfa-2a (PEG-IFN)
The preclinical toxicology data demonstrate that the modification of the interferon alfa-2a (IFN) molecule by pegylation (PEG-IFN) does not induce additional or unexpected toxicity beyond that previously observed with interferons. The following were the main findings:
A 4-week toxicity study was performed in cynomologus monkeys using twice weekly sc dosing to give dose levels of 30, 375, and 1125 mcg/kg/week. Only mild effects were observed and these were limited to transient clinical pathology changes at the mid and high doses. Toxicological findings were limited to the following: slight transient hematological changes (i.e., decreased platelet and WBC counts) and slight transient clinical chemistry changes, including decreases in protein, calcium, and, in a few animals, elevated ALT and/or AST (1.4 to 2.3 times baseline) values. In a 13-week study of similar design, comparable results for the decreases in platelets, WBC and protein were seen at all three dose levels (30, 100 and 300 mcg/kg/week).
The toxicity profile of PEG-IFN was further characterized in a 4-week daily dose study employing sc doses of 15, 100, and 600 mcg/kg/day. Changes similar to those described above but with more pronounced effects were observed. In one female monkey receiving 600 mcg/kg/day, pronounced adverse effects, clinical signs, and clinical pathology changes (regenerative anemia, leukopenia, thrombocytopenia, and increases in liver function chemistry) were seen that required dosing to be discontinued. Upon resumption of dosing, these effects did not reappear. No histopathologic findings occurred in any multiple-dose toxicity study.
PEG-IFN is less immunogenic than IFN in mice. PEG-IFN and IFN were comparably immunogenic in monkeys. As a consequence of an immunogenic response to PEG-IFN by monkeys, which results in a marked reduction in serum exposure to PEG-IFN, a resolution of adverse effects was observed during the treatment period in all multiple-dose studies. The immunogenic response of monkeys to PEG-IFN was expected, as human interferons are known to be immunogenic in other animal species. Effects of treatment beyond 4 weeks could not be accurately assessed in the animal models as a result of their immunogenic response.
Despite the marked reduction in serum exposure with time, the exposure in animals (AUC, Cmax) remained considerably higher than that seen in patients.
During all toxicity studies, a mild subcutaneous inflammatory reaction occurred at the injection sites of both PEG-IFN and placebo-control animals. No histopathological findings are observed in any of the multiple-dose toxicity studies, with the exception of subcutaneous inflammation at the injection sites.
Carcinogenesis: Peginterferon alfa-2a has not been tested for its carcinogenic potential.
Mutagenesis: Peginterferon alfa-2a was neither mutagenic nor clastogenic when tested in the Ames bacterial mutagenicity assay and in the in vitro chromosomal aberration assay in human lymphocytes, either in the presence or absence of metabolic activation.
Impairment of Fertility: As with other alpha interferons, prolongation of the menstrual cycle accompanied by both a decrease and delay in the peak of 17ß-estradiol and progesterone levels have been observed following administration of peginterferon alfa-2a to female cynomolgus monkeys. A return to normal menstrual rhythm followed discontinuation of treatment. Similar effects in the monkey have previously been associated with the occurrence of spontaneous abortions in addition to impaired female fertility. Peginterferon alfa-2a has not been studied for its effect on male fertility. However, treatment with interferon alfa-2a did not affect fertility of male rhesus monkeys treated for 5 months at doses up to 25 x 106 IU/kg/day.
The toxicology studies performed with PEG-IFN are summarized in Tables 13 to 18.
Table 13 Peginterferon alfa-2a: Summary of Acute (Single-Dose) Toxicity Studies
| Title | Species/ Strain | No./ Sex/ Dose | Dose (μg/kg) | Duration of Observations/ Route of Administration | Maximum Non-Lethal Dose | Target Organs/ Systems of Toxicity |
| Acute Study | Monkeys/ Cynomolgus | one | 6750 | 14 days after final dosing Subcutaneous | > 6750 μg/kg (technical limit dose) | Clinical signs: piloerection in the male and unsteady gait in the female. Clinical Pathology: transient mild anemia and decrease in WBC. Elevated ALT and decrease in protein and albumin. Mild subcutaneous hemorrhage at one injection site |
| Acute Study | Monkeys/ Cynomolgus | one | 0, 15, 70, 300 | 14 days after final dosing Intravenous | > 300 μg/kg | Adverse effects were limited to bruising at the injection sites and transient elevation of AST in one monkey at the high dose |
Table 14 Peginterferon alfa-2a: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Monkeys:
4-Week Twice Weekly Subcutaneous Dosing Study
| Species/ Strain & No. Animals | ||||
| Dose (μg/kg dose) | ||||
| Day Sampled | Dose sampled | Mean [Serum] (ng/mL) | Mean Cmax ±SD (ng/mL) | Mean AUC0-72h (ng∙h/mL) |
| Treatment-Related Effects | ||||
| Neutralizing Antibody Titerb | ||||
Monkeys Cynomolgus 3/sex/group | ||||
| 15 | ||||
| 1 | 1 | 98 ±21 | 6000 | |
| No toxicity was observed. Total antibodies to IFN were present in 1 female on day 15 and in all monkeys at the end of the study. | ||||
| Median: 22.5 Range: 17.5-400 | ||||
| 15 | 4a | 46 | ||
| 26 | 8 | 184 ±320 | 9770 | |
| 187.5 | ||||
| 1 | 1 | 2050 ±263 | 130000 | |
| After 2 weeks of treatment, transient changes included: ↓mean protein (albumin, globulin fractions) and calcium level compared to pre-study. ↑ ALT in 2 males and AST in 1 male. No histopathologic findings were noted. Total antibodies to IFN were present in 1 male and 2 females on day 15 and in all monkeys at the end of the study. | ||||
Median: 60 Range: 30-400 | ||||
| 5 | 4a | 1818 | ||
| 26 | 8 | 203 ±178 | 13200 | |
| 562.5 | ||||
| 1 | 1 | 6565 ±1403 | 392000 | |
| Transient changes noted included: ↓ mean platelets prior to doses 3 and 5 in 1 male and 1 female; ↓ in WBC and neutrophil prior to dose 3; ↓mean protein and calcium prior to dose 5; ↑ ALT and AST in 1 male and 1 female, and ↑ absolute and relative liver and spleen weights. No histopathologic findings were noted. Total antibodies to IFN were present in all monkeys on day 15 and at the end of the study. | ||||
Median: 280 Range: 60-560 | ||||
| 15 | 4a | 113 | ||
| 26 | 8 | 328 ±169 | 22400 | |
a Samples 72 hours after dose 4 only.
b Samples 72 hours after last dose (dose 8). Neutralizing antibody titer is the reciprocal of the last dilution of serum that reduces the effective concentration of IFN alfa-2a from 10 U/mL to 1 U/mL.
Table 15 Peginterferon alfa-2a: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Monkeys:
4-Week Daily Subcutaneous Study with 4-Week Recovery Period
| Species/ Strain No. Animals | Dose (μg/kg/ day) | Dose sampled (day) | Meana [Serum] (ng/mL) | Meanb Cmax (ng/mL) | Meanb AUC0-24h (ng∙h/mL) | Treatment-Related Effects | Total Antibody Titer (IFN binding Units/mL) | Neutralizing Antibody Titerb | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Monkeys Cynomolgus 5/sex/ group | 15 | 1 2 4 8 9 11 16 18 23 25 29c | 133 419 1072 948 270 331 50 46 70 | 133 - - 1070 | 1970 - - 23700 | Transient changes that peaked at days 8 and/or 15 included: ↓ mean platelets that were significant only in males; ↓ WBC (neutrophils ); ↓ reticulocytes. ↑ APTT in some males and females. No histopathologic findings were noted. | Day 16 (Treatment) 1 of 10 monkeys = 1110 Day 29 (Treatment)c Median: 1632 Range: 0 - 8196 Day 16 (Recovery) Median: 795 Range: 580 - 2391 Day 29 (Recovery) Median: 753 Range: 0 - 1125 | Day 16 (Recovery) Median: 298 Range: 75 to 520 Day 29 (Recovery) Median: 210 Range: 130 to 480 | ||||||
| 100 | 1 2 4 8 9 11 16 18 23 25 29c | 1250 4776 8280 8693 778 390 251 169 199 | 1250 - - 9240 | 18800 - - 209000 | Transient changes that peaked at days 8 and/or 15 included: ↓ mean platelets that were significant only in males; ↓ WBC (neutrophils); ↓ reticulocytes; ↓ fibrinogen in males. ↑ APTT in some males and females. ↓ total protein. No histopathologic findings were noted. | Day 16 (Treatment) Median: 573 Range: 0 - 2228 Day 29 (Treatment)c Median: 3880 Range: 0 - 20475 Day 16 (Recovery) Median: 2657 Range: 608 - 4050 Day 29 (Recovery) Median: 2069 Range: 0 - 3833 | Day 16 (Recovery) Median: 800 Range: 640 to 960 Day 29 (Recovery) Median: 1880 Range: 1200 to 2560 | |||||||
| 600 | 1 2 4 8 9 11 16 18 23 25 29c | 6674 21445 48270 37113 684 365 329 631 572 | 6670 48900 | 102000 1120000 | Transient changes that peaked at days 8 and/or 15 included: ↓ mean platelets that was significant only in males; ↓ WBC (neutrophils); ↓ reticulocytes; ↓ fibrinogen in males; significant ↑ APTT. There was ↑ RDW on days 22 and at end of treatment period. At most time points minimal ↓ HCT, HGB, and RBC were seen in males. ↓ total protein. ↓ calcium and BUN in females. No histo-pathologic findings were noted. | Day 16 (Treatment) Median: 3678 Range: 0 – 9736 Day 29 (Treatment)c Median: 14031 Range: 486-54694 Day 16 (Recovery) Median: 9397 Range: 2601-18225 Day 29 (Recovery) Median: 5931 Range: 1145-11328 | Day 16 (Recovery) Median: 1840 Range: 400-4267 Day 29 (Recovery) Median: 880 Range: 760 to 8320 | |||||||
a Mean serum concentrations from samples obtained on specified days, prior to dosing. b Cmax and AUC0-24hr were calculated for sample days 1 and 8 of the treatment period. c Sampled 24 hours after the last dose (dose 28). d The neutralizing antibody titer is the reciprocal of the last dilution of serum that reduces the effective concentration of IFN alfa-2a from 20 units/mL to 1 unit/mL. | ||||||||||||||
Table 16 Peginterferon alfa-2a: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Monkeys:
13-Week Twice Weekly Subcutaneous Study with 4-Week Recovery Period
| Species/ Strain & No. Animals | Dose (μg/kg/dose) | Day Sampled | Dose sampled | Mean Cmax (ng/mL) | Mean AUC0-96h (ng∙h/mL) | Treatment-Related Effects | Day Sampled | Median Total Antibody Titera (IBU/mL) | Median Neutralizing Antibody Titera,b |
Monkeys Cynomol- gus 5/sex/ group | 15 | 0 - 14 - 28 - 56 - 84 | 1 - 5 - 9 - 17 - 25 | 161 110 86 196 426 | 11837 3679 7642 15182 36947 | Slight transient ↓ leukocytes, neutrophils, total protein & albumin. Slight hemorrhage and inflammation at injection sites | 33 - 61 - 92 - 103 - 117 | 543 (154-972) 391 (0-783) 428 (0-823) 426 (225-528) 202 (144-323) | 80 (40-320) 800 (0-800) 1600 (0-6400) 2400 (1600-3200) 6400 (1600-12800) |
| 50 | 0 - 14 - 28 - 56 - 84 | 1 - 5 - 9 - 17 - 25 | 515 425 114 455 819 | 40643 23508 9819 36135 69168 | Slight transient ↓ platelets, leucocytes, neutrophils, total protein & albumin. Slight transient ↑fibrinogen. Slight hemorrhage and inflammation at injection sites | 33 - 61 - 92 - 103 - 117 | 814 (367-1350) 692 (204-1070) 740 (223-1330) 535 (187-1270) 245 (0-980) | 200 (80-800) 1600 (400-12800) 2400 (1600-12800) 6400 (3200-12800) 9600 (1600-12800) | |
| 150 | 0 - 14 - 28 - 56 - 84 | 1 - 5 - 9 - 17 - 25 | 1445 423 228 1284 2545 | 117626 36424 17798 104849 226566 | Slight transient ↓ platelets, leukocytes, neutrophils, prothrombin time, total protein & albumin. Slight transient ↑ APTT & fibrinogen. Slight transient ↑ ALT (2 animals), Slight hemorrhage and inflammation at injection sites | 33 - 61 - 92 - 103 - 117 | 959 (702-1130) 919 (663-1270) 1270 (982-5010) 1010 664 (358-812) | 180 (0-3200) 2400 (100-12800) 8000 (200-12800) 6400 (1600-12800) 12800 (3200-12800) | |
| a Range of observed values appears in brackets b The neutralizing antibody titers are reported as the reciprocal of the last dilution of antiserum that neutralizes IFN alfa-2a from 10 lab units/mL to 1 lab unit/mL. | |||||||||
Table 17 Summary of Pilot Study on the Effects of Peginterferon alfa-2a on Sex Steroid Hormones in Female Monkeys
| Species/ Strain No. of Animal | Dose (μg/kg/dose) Regimen | Duration/ Route of Administration | Treatment-Related Effects |
Cynomolgus Monkeys 2 females/ group | 100, 300, 600 3 times/week Roferon-A (positive control): 25 MIU/kg, daily | Subcutaneous administration over 1 menstrual cycle or maximum of 6 weeks Roferon-A (positive control): intramuscular | Low Dose: no adverse effects |
| Mid Dose: prolonged menstrual cycle (1 of 2), with delayed peak of 17β-estradiol and progesterone levels. | |||
| High Dose: menstruation not observed (amenorrhea) in one of 2 females, with delayed peak of 17β-estradiol and progesterone levels. Interferon alfa-2a: prolonged menstrual cycle (2 of 2), with delayed peak of 17β-estradiol and progesterone levels. | |||
Table 18 Summary of Study on the Effects of Peginterferon alfa-2a on Sex Steroid Hormones in Female Monkeys with a Recovery Period
| Species/ Strain & No. Animals | Dose (μg/kg/ dose) | Duration/ Route/ Regimen | Dose sampled | Mean Cmax ±SD (ng/mL) | Mean AUC0-48h±SD (ng∙h/mL) | Median Neutralizing Antibody Titerb | Treatment-Related Effects |
|---|---|---|---|---|---|---|---|
Monkeys Cynomolgus 5 females/ group | Interferon alfa-2a: 25 MIU/kg/day | Daily IM administered over 1 menstrual cycle or maximum of 6 weeks. Recovery period of 1 menstrual cycle. | 96 hr after last dose: Median: 2000 Range: 1000-32000 20 days after last dose: Median: 4000 Range: 1000-32000 | Prolonged menstrual cycle (4 of 5 monkeys), with a decrease and a delay in the peak of 17β-estratidiol and progesterone levels. Changes were reversible. Mean cycle lengthc: Dosing period: 39.2 d Recovery period: 32.6 d | |||
| 100 | 3 time/week SC administration over 1 menstrual cycle or maximum of 6 weeks. Recovery period of 1 menstrual cycle. | 1 4 7 Last Dose | 1650±284 3540±743 1410±3020 2000±2280 | 53400±13800 159000±30200 43000±91100 98600±104000a | 96 hr after last dose: Median: 1600 Range: 400-51200 20 days after last dose: Median: 3200 Range: 200-51200 | Prolonged menstrual cycle (2 of 5 monkeys), with a decrease and a delay in the peak of 17β- estradiol and progesterone levels. Changes were reversible. Mean cycle lengthc: Dosing period: 41.0 d Recovery period: 31.2 d | |
| 600 | 3 time/ week SC administration over 1 menstrual cycle or maximum of 6 weeks. Recovery period of 1 menstrual cycle. | 1 4 7 Last Dose | 8870±2560 24400±7910 197±178 2050±1230 | 298000±79700 1060000±318000 5410±3190 138000±105000a | 96 hr after last dose: Median: 6400 Range: 3200-12800 20 days after last dose: Median: 12800 Range: 3200- 12800 | Prolonged menstrual cycle (5 of 5 monkeys), with a decrease and a delay in the peak of 17β- estradiol and progesterone levels. Changes were reversible. Mean cycle lengthc: Dosing period: 61.8 d Recovery period: 28.8 d | |
| a Last dose values represent from mean AUC0-96 h. b The neutralizing antibody titers are reported as the reciprocal of the last dilution of antiserum that neutralizes IFN alfa-2a from 10 lab units/mL to 1 lab unit/mL. c Mean cycle length (Vehicle control): Dosing period:27.8 d; Recovery period:28.0 d | |||||||
Peginterferon alfa-2a and Ribavirin Combination
A four-week toxicity study with combination therapy was conducted in cynomologous monkeys. The findings from this study are summarized in Table 19. At a dose of 100 mg/kg/day of ribavirin alone, effects on the erythron indicative of a mild anemia were observed. These effects were slightly more severe in monkeys treated with 600 mcg/kg/dose of PEG-IFN alfa-2a twice weekly plus 100 mg/kg/day of ribavirin. These doses are 400 times the intended weekly clinical dose of PEG-IFN alfa-2a (180 mcg/week, 3 mcg/kg for a 60-kg person) and approximately six times the intended daily clinical dose of ribavirin (1000 mg/day for a 60-kg person or 16 mg/kg/day).
Animals treated with 50 mg/kg/day of ribavirin alone exhibited no effects on the erythron. Animals administered 600 mcg/kg of PEG-IFN alfa-2a twice weekly plus 50 mg/kg/day of ribavirin exhibited decreases in red blood cell (RBC) parameters.
Bone marrow cytology and microscopic evaluations showed erythroid hypoplasia for one of 10 animals treated with 600 mcg/kg of PEG-IFN alfa-2a twice weekly plus 50 mg/kg/day of ribavirin and for two of 10 animals treated with 600 mcg/kg of PEG-IFN alfa-2a twice weekly plus 100 mg/kg/day of ribavirin.
No new or unexpected toxicities were observed for animals treated with the combination therapy compared with animals treated with ribavirin or PEG-IFN alfa-2a alone.
Table 19 PEGASYS + Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Monkeys
- Twice Weekly Subcutaneous Dosing (PEGASYS) and Daily Oral (Gavage) Dosing (Ribavirin) Study
| Species/ Strain and No. Animals | Dose | Day of | Ro 20-9963 in Serum | Ro 20-9963 in Blood | Ro 25-8310 in Serum | ||
| (mg/kg/day) | |||||||
| Sampling | Cmax | AUC1-24 | Cmax | AUC1-24 | Cmax | ||
| AUC1-48 | SNF | ||||||
| Treatment-related Effect | |||||||
| (ng/mL) | (ng hr/mL) | (ng/mL) | (ng hr/mL) | (ng/mL) | (ng hr/mL) | Nu/mL | |
| Cynomo- logus monkeys | |||||||
| 50 – Rib | |||||||
| 1 | 383 | 5800 | 2630 | 29700 | |||
Discolored urine, Slight ↓Body wt. & Food consumption, ↓cholesterol | |||||||
| 15 | 1510 | 2580 | 3320 | 60600 | |||
| 29 | 1700 | NA | 25900 | 141000 | |||
| (5/sex/ group- main study;#2 /sex/ group- TK) | |||||||
| 100 – Rib | |||||||
| 1 | 474 | 7060 | 1810 | 23400 | |||
Dehydrated appearance, Slight↓ Body wt. & Food consumption, ↓ erythrocytes, hemoglobin, hematocrit, ↑ reticulocytes, ↓cholesterol, erythroid hyperplasia - bone marrow cytology | |||||||
| 15 | 3120 | 51100 | 50100 | 565000 | |||
| 29 | 2810 | 52200 | 38900 | 695000 | |||
| 600 - PEG | |||||||
| 38 | 80- >640 | ||||||
| Dehydrated appearance, Discolored urine, ↓ Feces, Slight ↓ Body wt. & Food consumption, | |||||||
| 54 | 320- >640 | ||||||
| slight transient ↓ erythrocytes, hemoglobin, hematocrit, ↑reticulocytes, ↓WBC, platelets, neutrophils, ↓ total protein, albumin, globulin, total bilirubin, calcium, phosphorus | |||||||
| 50 – Rib + 600 - PEG | |||||||
| 1 | 214 | 4860 | 394 | 7790 | 10500 | 297000 | |
| Dehydrated appearance, Discolored urine, ↓ Feces, Slight↓ Body wt. & Food consumption, ↓ erythrocytes, hemoglobin, hematocrit, ↑ reticulocytes, ↓ WBC, platelets, neutrophils, ↓ total protein, albumin, globulin, total bilirubin, calcium, phosphorus, erythroid hyperplasia - bone marrow cytology, erythroid hypoplasia - bone marrow cytology and histopathology | |||||||
| 15 | 1460 | 26500 | 2910 | 54600 | 2830 | 54700 | |
| 29 | 1470 | 23000 | 51200 | 159000 | 307 | 9380 | |
| 38 | 80- >640 | ||||||
| 54 | >640 | ||||||
| 100 – Rib + 600 - PEG | |||||||
| 1 | 931 | 14000 | 1250 | 24100 | 11100 | 360000 | |
| Dehydrated appearance, Discolored urine, ↓ Feces, Slight ↓ Body wt. & Food consumption, ↓ erythrocytes, hemoglobin, hematocrit, ↑ reticulocytes, ↓WBC, platelets, neutrophils, ↓ cholesterol, ↓ total protein, albumin, globulin, total bilirubin, calcium, phosphorus, erythroid hypoplasia - bone marrow cytology and histopathology | |||||||
| 15 | 2550 | 51800 | 56000 | 590000 | 33200 | 1030000 | |
| 29 | 3710 | 59100 | 66000 | 415000 | 1180 | ||
| NA | |||||||
| 38 | 40- >640 | ||||||
| 54 | >640 | ||||||
| Rib = Ro 20-9963 (ribavirin), PEG = Ro 25-8310 (pegylated interferon alfa 2-a) SNF = Serum Neutralization Factor, NA = not available due to the death of 1 female on Day 28. | |||||||
Ribavirin
At all doses tested in the repeat-dose rodent studies, effects on the erythron (reduced RBC counts, hemoglobin, and/or hematocrit) were noted. At the higher doses tested, these effects were indicative of anemia. In dogs, slight effects on the erythron were noted only at the highest dose tested (20 mg/kg/day). The effects on the erythron were similar to those reported in the literature for monkeys and patients following administration of ribavirin.
Histopathology findings that correlated with the effects on the erythron included extramedullary splenic hematopoiesis in rodents and hypercellularity of the femur marrow in rats. Erythroid hypoplasia in the bone marrow was observed in decedent mice at 200 and 400 mg/kg/day in a 4-week study and in rats at the highest dose of 160 mg/kg/day in a 13-week study.
Decreased leucocyte and/or lymphocyte counts were observed at relatively high doses in rodents and at all tested doses (5 to 20 mg/kg/day) in dogs.
Consistent with the literature, lymphoid depletion was noted microscopically at most of the tested doses in the rodent studies.
Gastrointestinal effects (crypt cell necrosis and reduced number of epithelial cells) were noted in rodents that died prematurely. Similar findings and chronic inflammation and erosion were also noted for dogs treated at 10 and 20 mg/kg/day.
The majority of the effects noted in the repeat-dose studies with ribavirin were reversible upon treatment withdrawal.
The toxicity studies performed with ribavirin are summarized in Tables 20 to 24.
Table 20 Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Mice: 4-Week Daily Oral (Gavage)
Dosing Study
| Species/ Strain & No. Animals | Dose (mg/kg/day) | Mean Cmax (ng/mL) | Mean AUC0-24hr (ng∙hr/mL) | Mean blood conc. [Mean RBC conc.] (ng/mL)* | Treatment-Related Effects |
Mice CD-1 10/sex/ group-main study; 24/sex/dose level and 6/sex-controls; toxicokinetic animals | 30 | 1148 | 11591 | 77.9 [77.3--mean of 4 animals] | ↓ erythrocytes (males), ↓ alanine aminotransferases (males), ↑ splenic extramedullary hematopoiesis |
| 100 | 3394 | 35490 | 184 [171-1 animal only] | ↓ erythrocytes, ↓ hemoglobin, ↓ hematocrit, ↑ platelets, ↓ alanine aminotransferases, ↑ splenic extramedullary hematopoiesis | |
| 200 | 4585 | 71887 | 440 [563-1 animal only] | ↑ mortality, ↓ erythrocytes, ↓ hemoglobin, ↓hematocrit, ↓ leukocytes ↓ lymphocytes, ↑platelets, ↓ alanine and aspartate aminotransferases, ↓ relative testes and epididymis weight,↑ absolute and relative spleen weight, ↑ splenic extramedullary hematopoiesis, the following noted in animals that died: crypt cell necrosis and regenerative hyperplasia in the small and large intestine; lymphoid depletion/necrosis in the thymus, spleen, and mesenteric lymph node; adrenal cortical hypertrophy, atrophy of salivary glands, congestion and hypocellularity in the bone marrow; and hypospermia in the epididymis | |
| 400 | 19570 | NA (males) 142513 (females) | NA | ↑ mortality (all animals died); ↓ erythrocytes, ↓ hemoglobin, ↓ hematocrit, ↓ leukocytes, ↓ lymphocytes, ↑ platelets, ↓ alanine and aspartate aminotransferase, crypt cell necrosis and regenerative hyperplasia in the small and large intestine; lymphoid depletion/necrosis in the thymus, spleen, and mesenteric lymph node; adrenal cortical hypertrophy, atrophy of salivary glands, congestion and hypocellularity in the bone marrow; and hypospermia in the epididymis | |
| NA = Not Available Note: Samples from 30, 100 and 200 mg/kg/day groups were collected on dosing days 28 and 29 while samples from the 400 mg/kg/day group were collected on day 12. *Ribavirin concentrations in whole blood samples and erythrocytes were determined from samples obtained 24 hours after the last dose (Study Day 29). Because animals in Group 5 died or were sacrificed on or before Day 12, ribavirin concentrations in whole blood were not obtained for Group 5 animals. | |||||
Table 21 Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Rats: 13-Week Daily Oral (Gavage) Dosing Study
| Species /Strain and No. Animals | |||
| Dose (mg/kg/day) | |||
| Day of Sampling | Serum | Mean blood conc. (ng/mL) | Mean RBC conc. (ng/mL) |
| Treatment-related Effect | |||
| Cmax (ng/mL) | AUC0-24 (ng∙hr/mL) | Males | Females |
Wistar rats 12/sex/ group-main study; 15/sex/ group- toxicokinetics | |||
| 10 | |||
| 1 | 112 | 1044 | 2 |
NR 15.5 27.2 | |||
19.7 6.4 17.7 | |||
| ↓ Hemoglobin and ↓ hematocrit | |||
| 28 | 145 | 1969 | 17 |
| 91 | 132 | 1861 | 24 |
| 40 | |||
| 1 | 363 | 5625 | 25 |
NR NR 54.7 | |||
NR 91.8 128 | |||
↓ Hemoglobin, ↓ hematocrit, thymic lymphoid depletion, ↓ thymic weights and skin lesions | |||
| 28 | 539 | 8681 | 65 |
| 91 | 538 | 8952 | 119 |
| 80 | |||
| 1 | 700 | 9930 | 65 |
| NR | |||
| NR | |||
↓ Body weight, ↓ body weight gain, ↓ food consumption, skin sores/scabs, ↓ erythrocytes, ↓ hemoglobin, ↓ hematocrit, ↑ platelet counts, ↓ cholesterol, ↑ inorganic phosphorus, ↓ thymic weights, skin lesions, and thymic lymphoid depletion | |||
| 28 | 858 | 13584 | 157 |
| NR | |||
| 14.8 | |||
| 91 | 947 | 16842 | 244 |
| 104 | |||
| 130 | |||
| 160 | |||
1 28 91 | 1202 2022 2809 | 16963 35908 46350 | 151 636 936 |
17.8 388 487 | |||
45.8 172 1041 | |||
| Mortality, hunched appearance, thin appearance, hypoactivity, sensitive to touch, vocalization, nasal discharge, few, liquid and no feces, pale eyes, audible, irregular and labored respiration, pale ears and body, skin sores/scabs, cold to touch (entire body), ↓ body weight, ↓ body weight gain, ↓ food consumption, ↓ erythrocytes, ↓ hemoglobin, ↓ hematocrit, ↑ reticulocyte counts, ↑ platelet counts, ↓ absolute lymphocyte counts, ↑ M/E ratio and erythroid hypoplasia (bone marrow cytology), ↑ prothrombin time, ↓ activated partial thromboplastin time, ↓ total protein, ↓ albumin, ↓ globulin, ↑ albumin-to-globulin ratio, ↓ cholesterol, ↓ triglycerides, ↑ aspartate aminotransferase, ↑ inorganic phosphorus, ↑ heart, lung and spleen weights, ↓ thymic weights, crusted areas of skin, skin lesions, thymic lymphoid depletion, depletion of thymus-dependent areas of spleen and mesenteric lymph nodes, ↓ number of erythroid and myeloid precursors in bone marrow, extramedullary hematopoiesis, ↑ foamy alveolar macrophages, hepatocellular degeneration and necrosis, hepatic pigment, and ↓ number of epithelial cells on the GI mucosa (unscheduled sacrifice-males) | |||
| NR=Not reported due to negative erythrocyte concentrations of Ro 20-9963. | |||
Table 22 Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Mice: 26-Week Daily Oral (Gavage) Dosing Study
| Species/ Strain and No. Animals | Dose (mg/kg/day) | Day of Sampling | Serum | Treatment-Related Effects |
| Cmax (ng/mL) | AUC0-24hr (ng∙hr/mL) | |||
P53 N5 hetero-zygous (+/-) mice (20/sex/group)
C57BL/6 mice (66/sex/group) -TK | ||||
| 10 | 1 | 1145 | 6305 | No treatment-related effects were observed |
| 183 | 893 | 6520 | ||
| 50 | 1 | 2500 | 21500 | ↓ Hemoglobin, ↑ red cell distribution width, |
| 183 | 3180 | 23150 | ↓ testes/epididymis weights (absolute and relative) | |
| 100 | 1 | 3706 | 29400 | ↓ Hemoglobin, ↓ Hematocrit, ↑ red cell distribution width, ↓ testes/epididymis weights (absolute and relative), ↓ spleen weight (absolute and relative) |
| 183 | 3810 | 33800 | ||
| *An increased trend for mortality and an increased trend for splenic and thymic lymphoid depletion was observed in males. | ||||
Table 23 Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Rats (26-Week Daily Oral (Gavage) Dosing Study)
| Species/Strain and No. Animals | Dose (mg/kg/day) | Day of Sampling | Serum | Mean Blood | Mean RBC conc. (ng/mL) | ||||||||||||||||||
| Cmax (ng/mL) | AUC0-24hr (ng∙hr/mL) | conc. (ng/mL) | Males | Females | Treatment-related Effects | ||||||||||||||||||
| Wistar rats | 10 | 1 | 100 | 1162 | 8 | 10.2 | 10.7 | ↓ Hemoglobin, ↓ hematocrit, ↑ platelet counts and thymic lymphoid depletion | |||||||||||||||
| 28 | 165 | 2170 | 18 | 3.4 | 8.5 | ||||||||||||||||||
| 20/sex/ | 91 | 226 | 2259 | 21 | 5.3 | 22.7 | |||||||||||||||||
| group-main study; | 126 | 205 | 2260 | 23 | 10.9 | 16.2 | |||||||||||||||||
| 182 | 199 | 2264 | 21 | 1.68 | 9.5 | ||||||||||||||||||
| 15/sex/ group- toxicokinetics | 35 | 1 | 324 | 4054 | 30 | 6.7 | 4.9 | ↑ Skin sores/scabs, ↓ hemoglobin, ↓ hematocrit, ↑ platelet counts, ↓ alanine aminotransferase activity, crusted regions of skin, skin ulceration (histologic), thymic lymphoid depletion, and hypercellularity of femur marrow | |||||||||||||||
| 28 | 457 | 6186 | 60 | 21.6 | 11.8 | ||||||||||||||||||
| 91 | 490 | 7149 | 72 | 33.9 | NR | ||||||||||||||||||
| 126 | 612 | 8521 | 89 | 47.2 | 18.0 | ||||||||||||||||||
| 182 | 537 | 7925 | 69 | 18.0 | 5.1 | ||||||||||||||||||
| 70 | 1 | 663 | 8744 | 67 | 9.4 | 1.7 | Mortality, ↑ skin sores/scabs, ↑ audible respiration, ↓ body weight,↓ body weight gain, ↓ food consumption, ↓ erythrocyte counts, ↓ hemoglobin, ↓ hematocrit, ↑ platelet counts, ↑ absolute and relative reticulocyte counts, ↓ cholesterol, ↑ inorganic phosphorus, ↓ alanine aminotransferase activity, crusted regions of skin, skin ulceration (histologic), small thymus , ↓ thymus weights, thymic lymphoid depletion, hypercellularity of femur marrow, extramedullary hematopoiesis in spleen, and hepatic pigment deposition | ||||||||||||||||
| 28 | 887 | 6857 | 141 | 49.4 | 57.0 | ||||||||||||||||||
| 91 | 1007 | 17244 | 205 | 74.2 | 41.9 | ||||||||||||||||||
| 126 | 1297 | 21460 | 265 | 81.7 | 103 | ||||||||||||||||||
| 182 | 1138 | 19152 | 197 | 30.0 | 71.8 | ||||||||||||||||||
| NR= Not reported due to negative erythrocyte concentrations of Ro 20-9963. | |||||||||||||||||||||||
Table 24 Ribavirin: Summary of Multiple-Dose Toxicity and Toxicokinetic Studies in Dogs: 26-Week Daily Oral (Gavage) Dosing Study
| Species/Strain and No. Animals | Dose (mg/kg/day) | Day of Sampling | Serum | Mean Blood | Mean RBC conc. (ng/mL) | |||||||||||||||
| Cmax (ng/mL) | AUC0-24hr (ng•hr/mL) | conc. (ng/mL) | Males | Females | Treatment-related Effects | |||||||||||||||
Beagle dogs 7/sex/ group | 5 | 1 | 1495 | 8315 | 37.9 | NR | NR | ↓ Mean lymphocyte counts | ||||||||||||
| 28 | 1180 | 9200 | 102.7 | 96.5 | 95.1 | |||||||||||||||
| 91 | 1555 | 9795 | 73.1 | 1.8 | 58.3 | |||||||||||||||
| 182 | 1605 | 10395 | 97.7 | 53.4 | 84.5 | |||||||||||||||
| 10 | 1 | 3170 | 17600 | 86.1 | 22.2 | 15.3 | ↓ Mean lymphocyte counts, dilatation/necrosis of intestinal crypts (duodenum) | |||||||||||||
| 28 | 2855 | 18550 | 142.5 | 61.0 | 81.9 | |||||||||||||||
| 91 | 3405 | 19450 | 202.5 | 89.8 | 345 | |||||||||||||||
| 182 | 3700 | 23100 | 174.5 | 74.8 | 78.5 | |||||||||||||||
| 20 | 1 | 7175 | 35700 | 236.5 | 18.2 | 205 | Fecal alterations, ↓ mean body weight (up to Week 4), ↓ body weight gain (up to Week 4), ↓ food consumption (up to Week 4), ↓ mean lymphocyte counts, ↓ WBCs, ↓ erythrocyte counts, ↓ hemoglobin, ↓ hematocrit, ↑ reticulocytes, ↓ alanine aminotransferase activity, ↓ total protein, ↑ pigment in the red pulp of the spleen, pigment deposition in Kupffer cells of the liver, ↑ dilatation/necrosis of intestinal crypts (duodenum), erosion of ileum,chronic inflammation of small intestine | |||||||||||||
| 28 | 6888 | 42600 | 386 | 250 | 286 | |||||||||||||||
| 91 | 7175 | 40450 | 273.5 | NR | NR | |||||||||||||||
| 182 | 6145 | 40050 | 358 | 121 | 152 | |||||||||||||||
| NR= Not reported due to negative erythrocyte concentrations of Ro 20-9963. | ||||||||||||||||||||
Carcinogenesis: Results from a 6-month alternative (p53 (+/-) mouse) carcinogenicity study and a rat 2-year carcinogenicity study showed no treatment-related increase in the incidence or severity of any neoplastic lesion up to the maximum tolerated dose of 100 mg/kg/day (sixfold higher than the therapeutic dose) and 60 mg/kg/day, respectively. On a body surface area basis, these doses are approximately 0.5 and 0.6 times the maximum recommended human 24-hour dose of ribavirin. The 100 mg/kg/day dose level resulted in an AUC0-24hr of 34 mcg∙hr/mL. The therapeutic AUC0-12hr for ribavirin was 26.4 mcg∙hr/mL (calculated from samples collected after the morning dose of ribavirin), which was similar to the exposure at the highest dose tested in the mouse study, which resulted in no treatment-related neoplasia.
Mutagenesis: Ribavirin was tested negative in the Ames mutagenicity assay, positive in the in vitro mouse lymphoma assay, and negative in the in vivo micronucleus assay. See Table 25.
Table 25 Ribavirin: Summary of Mutagenicity and Genotoxicity Studies
| Title | Assay System | Concentration/ Dose of Ribavirin Administered | Duration of Exposure | Genotoxic and Other Findings |
| Bacterial Cell Gene Mutation | Ames Test: standard plate incorporation method using strains TA98, 100, 1535 & 1537 of Salmonella typhimurium, and strain WP2uvrA of Escherichia coli with and without metabolic activation | 3.33 to 5000 μg/plate (Salmonella typhimurium); 10.00 to 5000 μg/plate (Escherichia coli) | 2 days | No mutagenic activity observed with or without metabolic activation. |
| Mouse Lymphoma (in vitro) | Mouse lymphoma L5178Y cell line | 7.85 to 2500 μg/ml | 4-hour treatment period | Positive without activation; Weak positive with activation |
| In vivo mouse micronucleus | Polychromatic erythrocytes (PCEs) from CD-1 mouse bone marrow | 500, 1000, 2000 mg/kg/day | 3 days | ↓ PCE:NCE ratio at all doses indicating cytotoxicity to bone marrow; no ↑ in micronucleated PCEs (negative) |
Reproduction Studies
No reproductive toxicology studies have been performed using PEGASYS in combination with COPEGUS (ribavirin). The collective data indicate that PEG-IFN alfa-2a and ribavirin combination therapy is a reproductive toxicant and teratogen. Effects on reproductive parameters can be attributed to both PEG-IFN alfa-2a and ribavirin. These effects are expected to be fully reversible after treatment discontinuation. The teratogenic potential of the combination therapy is attributed to the known teratogenic potential of ribavirin.
Extensive data are available in the literature with regard to the teratogenic potential of ribavirin. These data indicate that ribavirin is teratogenic in all rodent species tested (mice, rats, and hamsters) following single or multiple dose administration. The dose of ribavirin that induced teratogenic effect was as low as 2.5 mg/kg. In non-rodent species (rabbits and baboons), a definitive assessment of the teratogenic potential of ribavirin could not be made due to the inadequate design of the published studies.
Results from a segment I study in rats (Table 26) for investigating the effect of ribavirin on fertility showed an increase in preimplantation loss and resorption rates in female animals from the mid-dose (30 mg/kg/day) and high-dose (100 mg/kg/day) groups. These results were consistent with ribavirin’s inhibitory effects on rapidly proliferating cells and confirmed that ribavirin is embryotoxic.
Results from the segment I study also showed a marginal reduction in sperm counts in male animals receiving high ribavirin dose. The fertility of the untreated female animals, who mated with the ribavirin-treated male animals with reduced sperm counts, was not affected. The ribavirin-induced reduction in sperm counts is consistent with findings in literature, which reports decreased spermatid counts and sperm motility and increased abnormal sperm following oral administration of ribavirin to mice at 35, 75, and 150 mg/kg for up to 6 months. Additionally, histopathological changes, including degeneration of the seminiferous tubular epithelium primarily characterized by vacuolization, reduced thickness, and necrosis of germinal cells were also reported previously in animals treated with ribavirin at doses ≥35 mg/kg/day. Although no treatment-related findings of histopathology were noted in the segment I fertility study in rats, hypospermia in the epididymis was observed microscopically in male mice that died prematurely. These mice were treated with ribavirin doses of 200 and 400 mg/kg/day in a 4-week repeat-dose study. Published data showed that upon cessation of treatment, a complete recovery from the testicular toxicity was apparent within one to two spermatogenesis cycles. Similarly, reduced sperm counts were shown to be reversible after a 9-week recovery period in the segment I fertility study in rats.
Table 26 Ribavirin: Summary of Reproductive Toxicity Studies: Fertility Oral (Gavage) Dosing
| Species/Strain and No. Animals | Serum | Treatment-Related Effects | ||
| Dose (mg/kg/day) | Duration | Cmax (ng/mL) | AUC0-24hr (ng∙hr/mL) | |
Sprague-Dawley rats 20 females/group: main study; mated with untreated males 11 females/group: Toxicokinetics | ||||
| 10 | 4 weeks before mating, through gestation day 7 | 279 (day 0) 291 (day 27) | 1420 (Day 0) 1970 (Day 27) | |
| 30 | 4 weeks before mating, through gestation day 7 | 484 (day 0) 439 (day 27) | 4220 (Day 0) 4940 (Day 27) | ↑ preimplantation loss; ↑ resorption rate |
| 100 | 4 weeks before mating, through gestation day 7 | 1230 (day 0) 1380 (day 27) | 15200 (Day 0) 18300 (Day 27) | ↓ maternal food consumption; ↑ pre-implantation loss; ↑ resorption rate; ↓ live litter size |
Sprague-Dawley rats 20 females/group: main study; mated with untreated males (recovery) | ||||
| 10 | 4 weeks + 6 weeks of no treatment prior to mating | |||
| 30 | 4 weeks + 6 weeks of no treatment prior to mating | |||
| 100 | 4 weeks + 6 weeks of no treatment prior to mating | ↓ body-weight gain during treatment; ↓ food consumption during treatment | ||
Sprague-Dawley rats 20 males/group: main study; mated with untreated females 11 males/group: Toxicokinetics | ||||
| 10 | 9 weeks before and through mating | 304 (day 0) 219 (day 62) | 1700 (Day 0) 1970 (Day 62) | |
| 30 | 9 weeks before and through mating | 954 (day 0) 839 (day 62) | 6310 (Day 0) 6770 (Day 62) | ↓ body-weight gain during treatment |
| 100 | 9 weeks before and through mating | 2010 (day 0) 1470 (day 62) | 17600 (Day 0) 18200 (Day 62) | ↓ body-weight gain during treatment; ↓ food consumption during treatment; ↓ sperm count |
Sprague-Dawley rats 20 males/group: main study; mated with untreated females (recovery) | ||||
| 10 | 11 weeks + 9 weeks of no treatment prior to mating | |||
| 30 | 11 weeks + 9 weeks of no treatment prior to mating | |||
| 100 | 11 weeks + 9 weeks of no treatment prior to mating | ↓ body-weight gain during treatment; ↓ food consumption during treatment | ||
REFERENCES
- 1. Bernstein D et al. Relationship of health-related quality of life to treatment adherence and sustained response in chronic hepatitis C patients. Hepatology 2002;35(3):704-708
- 2. Bonkovsky HL, Woolley JM. Reduction of health-related quality of life in chronic hepatitis C and improvement with interferon therapy. Hepatology. 1999;29:264-70
- 3. Bruchfeld A, Stahle L, Anderson J et al. Ribavirin treatment in dialysis patients with chronic hepatitis C virus infection - A pilot study. J Viral Hepat 2001 Jul;8(4)287-92
- 4. Charles SA, Harris JM, Pedder S, Kumar S. Improving hepatitis C therapy. Attaching a polyethylene glycol “tail” to interferon for better clinical properties. Modern Drug Discovery 2000:59-67
- 5. Doglio A. Second generation of the automated Cobas Amplicor HCV assay improves sensitivity of hepatitis C virus RNA detection and yields that are more clinically relevant. J Clin Microbiol 1999;37:1567-69
- 6. Fattovich G. A survey of adverse events in 11 241 patients with chronic viral hepatitis treated with alfa interferon. Journal of Hepatology 1996;24:38-47
- 7. Fleischer R, Boxwell D, et al. Nucleoside Analogues and Mitochondrial Toxicity. Clinical Infectious Diseases 2004; 38: e79-e80.
- 8. Fried MW, Shiffman, ML, Rajender Reddy K et al. Peginterferon alfa-2a plus ribavirin for chronic hepatitis C virus infection. N Engl J Med 2002;347(13):975-82
- 9. Frye RF. Validation of the five drug “Pittsburgh cocktail” approach for assessment of selective regulation of drug-metabolizing enzymes. Clin Pharmacol Ther 1997;62:365-76
- 10. Hadziyannis SJ et al. Peginterferon-α2a and ribavirin combination therapy in chronic hepatitis C. A randomized study of treatment duration and ribavirin dose. Ann Intern Med 2004;140:346-55
- 11. Heathcote EJ. Multinational evaluation of the efficacy and safety of once-weekly peginterferon alfa-2a (PEG-IFN) in patients with chronic hepatitis C (CHC) with compensated cirrhosis. Hepatology 1999;30(Suppl):316A
- 12. Heathcote EJ, Shiffman ML, Cooksley E. Peginterferon alfa-2a in patients with chronic hepatitis C and cirrhosis. N Eng J Med 2000;343(23):1673-724
- 13. Heathcote EJ. The pharmacokinetics of pegylated-40K interferon alfa-2a (PEG-IFN) in chronic hepatitis C (CHC) patients with cirrhosis. Gastroenterology 1999;116(Suppl);A735
- 14. Japour AJ. A Phase-I Study of the Safety, Pharmacokinetics, and Antiviral Activity of Combination Didanosine and Ribavirin in Patients with HIV-1 Disease. J Acquir Immune Defic Syndr Human Retrovirol 1996; 13:235-246
- 15. Jie K, Rensma PL, Veen S, Bosch FH, Valentijn RM. Safety of interferon and ribavirin therapy in haemodialysis patients with chronic hepatitis C: Results of a pilot study. Nephrol Dial Transplant 2001;16:193-5
- 16. Johnson EM. The effects of ribavirin on development and reproduction: a critical review of published and unpublished studies in experimental animals. J Am Coll Toxicol 1990;9:551-61
- 17. Knodell RG, Ishak KG, Black WC, et al. Formulation and applications of numerical scoring system for assessing histological activity in asymptomatic chronic active hepatitis. Hepatology 1981;1:431-35
- 18. Mauss S, Valenti W, et al. Risk factors for hepatic decompensation in patients with HIV/HCV coinfection and liver cirrhosis during interferon-based therapy. AIDS 2004 (18) No.13 F21-25.
- 19. McHutchinson JG, et al. Interferon alfa-2b alone or in combination with ribavirin as initial treatment for chronic hepatitis C. N Engl J Med 1998;339:1485-92
- 20. Product Monograph. Roferon-A® (Interferon alfa-2a, recombinant). Hoffmann-La Roche Limited. Date of Revision: July 22, 2002
- 21. Peck-Radosavljevic M. Blunted thrombopoietin response to interferon alfa-induced thrombocytopenia during treatment for hepatitis C. Hepatology 1998;28(5):1424-29
- 22. Reddy R et al. Controlled-release, pegylation, liposomal formulations: new mechanisms in the delivery of injectable drugs. Annals of Pharmacotherapy 2000;24:948-23
- 23. Reddy KR et al. Efficacy and safety of pegylated (40-kd) interferon alfa-2a compared with interferon alfa-2a in noncirrhotic patients with chronic hepatitis C. Hepatology 2001;33:433-438
- 24. Sata M. Mechanisms of thrombocytopenia induced by interferon therapy for chronic hepatitis. Br J Gastroenterology 1997;32:206-10
- 25. Sherman M, Bain V, Villeneuve JP, et al. Management of Viral Hepatitis: A Canadian Consensus Conference 2004. Available from: URL: www.hepatology.ca. Accessed August 16, 2004.
- 26. Sim SM et al. Effect of ribavirin on zidovudine efficacy and toxicity in vitro: a concentration-dependent interaction. AIDS Res Human Retrovir 1998;14(18):1661-1667
- 27. Stremlo D. Antiproliferative activity of pegylated interferon alpha (Ro 25-8310). Roche Research Report No. N-181539, February 2000
- 28. Torriani FJ, Rodriguez-Torres M, Rockstroh JK, et al. Peginterferon alfa-2a plus ribavirin for chronic hepatitis C virus infection in HIV infected patients. N Eng J Med 2004; 351 (5): 438-450.
- 29. Trepo C. Genotype and viral load as prognostic indicators in the treatment of hepatitis C. J Viral Hepatitis 2000;7(4):250-7
- 30. Trey C, Burns DG, Saunders SJ. Treatment of hepatic coma by exchange blood transfusion. N. Eng J Med. 274: 473-481, 1966.
- 31. Ware J. Health-related quality of life in chronic hepatitis C: impact of disease and treatment response. The Interventional Therapy Group. Hepatology 1999;30(2):550-5
- 32. Zeuzem S. Treatment of chronic hepatitis C virus infection in patients with cirrhosis. J Viral Hepatitis 2000;7(5):327-34
- 33. Zeuzem S, Feinman SV, Rasenack J et al. Peginterferon alfa-2a in patients with chronic hepatitis C. N Eng J Med 2000;343(23):1666-72
- 34. Zeuzem S et al. Viral kinetics in patients with chronic hepatitis C treated with standard or peginterferon alfa-2a. Gastroenterology 2001;120:1438-1447
- 35. Zeuzem S. Quantification of the initial decline of serum hepatitis C virus RNA and response to interferon alfa. Hepatology 1998;27:1149-56