


Product Monograph - PMS-Ramipril-HCTZ (Pharmascience, 2.5 mg / 12.5 mg, 5 mg / 12.5 mg, 5.0 mg / 25.0 mg)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Non-Medicinal Ingredients |
| Oral | Tablet -2.5 mg ramipril/12.5 mg hydrochlorothiazide -5 mg ramipril/12.5 mg hydrochlorothiazide -10 mg ramipril/12.5 mg hydrochlorothiazide -5 mg ramipril/25 mg hydrochlorothiazide -10 mg ramipril/25 mg hydrochlorothiazide | Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Lactose Monohydrate, Microcrystalline Cellulose and Sodium Stearyl Fumarate. In addition: The 5 mg/12.5 mg, 10 mg/12.5 mg & 10 mg/25 mg strengths also contain Red Iron Oxide. The 10 mg/12.5 mg strength also contains Yellow Iron Oxide. |
INDICATIONS AND CLINICAL USE
pms-RAMIPRIL-HCTZ (ramipril/hydrochlorothiazide) is indicated for the treatment of essential hypertension in patients for whom this combination therapy is appropriate.
pms-RAMIPRIL-HCTZ is not indicated for initial therapy (see DOSAGE AND ADMINISTRATION). Patients in whom ramipril and diuretic are initiated simultaneously can develop symptomatic hypotension.
Patients should be titrated on individual drugs. If the fixed combination represents the dose and dosing frequency determined by this titration, the use of pms-RAMIPRIL-HCTZ may be more convenient in the management of patients. If during maintenance therapy dosage adjustment is necessary, it is advisable to use the individual drugs.
Geriatrics (> 65 years)
There is limited clinical experience with ramipril and hydrochlorothiazide in the elderly (> 65 years) (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
Pediatrics (< 18 years)
The safety and effectiveness of ramipril and hydrochlorothiazide in children have not been established. Therefore pms-RAMIPRIL-HCTZ is not indicated in this patient population.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug, any other angiotensin converting enzyme inhibitor (ACE inhibitor), other thiazide diuretics, sulfonamides or any ingredient in the formulation or component of the container. For a complete listing of ingredients, see DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph
- Patients who have a history of hereditary/idiopathic angioedema with or without treatment with an ACE inhibitor (see WARNINGS AND PRECAUTIONS, Immune, Angioedema – Head and Neck)
Pregnant and nursing women (see WARNINGS AND PRECAUTIONS, Special
Populations, Pregnant Women and Nursing Women)
- Patients with haemodynamically relevant bilateral renal artery stenosis, or unilateral in the single kidney (see WARNINGS AND PRECAUTIONS, Renal, Renal Impairment)
- Patients with hypotensive states or hemodynamically unstable states
- Concomitant use with sacubitril/valsartan due to an increased risk of angioedema. Do not initiate pms-RAMIPRIL-HCTZ until at least 36 hours have elapsed following the last dose of sacubitril/valsartan. In the case of a switch from pms-RAMIPRIL-HCTZ to sacubitril/valsartan, do not start sacubitril/valsartan until at least 36 hours have elapsed following the last dose of pms-RAMIPRIL-HCTZ.
Combination with aliskiren-containing drugs in patients with
- diabetes mellitus (type 1 or type 2)
- moderate to severe renal impairment (GFR < 60 mL/min/1.73m2)
- hyperkalemia (> 5 mMol/L) or
- congestive heart failure who are hypotensive
(see WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System [RAS] and Renal; and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System [RAS])
Combination with angiotensin II receptor antagonists (ARBs) in patients with
- diabetes with end organ damage
- moderate to severe kidney insufficiency (GFR < 60 mL/min/1.73m2)
- hyperkalemia (> 5 mMol/L) or
- congestive heart failure who are hypotensive
(see WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System [RAS]; and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System [RAS])
- Combination with extracorporeal treatments leading to contact of blood with negatively charged surfaces since such use may lead to anaphylactoid reactions. Such extracorporeal treatments include dialysis or haemofiltration with certain high-flux (e.g., polyacrylonitrile) membranes and low-density lipoprotein apheresis with dextran sulfate (see WARNINGS AND PRECAUTIONS, Immune).
- Patients with anuria
- Patients with severe renal impairment (creatinine clearance <30 mL/min/1.73 m2)
- Patients on dialysis
- Patients with severe hepatic impairment
- Patients with clinically relevant electrolyte disturbances (e.g., hypokalemia, hyponatremia or hypercalcemia)
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
When used in pregnancy, angiotensin converting enzyme (ACE) inhibitors can cause injury or even death of the developing fetus. When pregnancy is detected, pms-RAMIPRIL-HCTZ (ramipril/hydrochlorothiazide) should be discontinued as soon as possible (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women).
General
Cough
A dry, persistent cough, which usually disappears only after withdrawal or lowering the dose of ramipril and hydrochlorothiazide tablets, has been reported. This is likely related to ramipril, the ACE inhibitor component of ramipril and hydrochlorothiazide tablets. Such a possibility should be considered as part of the differential diagnosis of cough (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Driving a Vehicle or Performing Other Hazardous Tasks
Some adverse effects (e.g., some symptoms of a reduction in blood pressure such as light-headedness, dizziness, syncope) may impair the patient's ability to concentrate and react and, therefore, constitute a risk in situations where these abilities are of particular importance (e.g., operating a vehicle or machinery).
Dual Blockade of the Renin-Angiotensin System (RAS)
There is evidence that coadministration of ACE inhibitors, such as the ramipril component in pms-RAMIPRIL-HCTZ, or of ARBs with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR < 60 mL/min/1.73m2). Therefore, the use of pms-RAMIPRIL-HCTZ in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS).
The use of pms-RAMIPRIL-HCTZ in combination with an ARB is contraindicated in patients with diabetic nephropathy (see CONTRAINDICATIONS).
Further, coadministration of ACE inhibitors, including the ramipril component of pms-RAMIPRIL-HCTZ, with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia (see DRUG INTERACTIONS).
Cardiovascular
Aortic Stenosis
There is concern, on theoretical grounds, that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Hypotension
Symptomatic hypotension has occurred after administration of ramipril, usually after the first or second dose or when the dose was increased. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, vomiting or in other situations in which a significant activation of the RAS is to be anticipated such as in patients with severe, and particularly malignant hypertension, in patients with hemodynamically relevant left-ventricular outflow impediment (e.g., stenosis of the aortic valve) or in patients with hemodynamically relevant renal artery stenosis. All patients should be cautioned that excessive perspiration and dehydration may lead to an excessive fall in blood pressure because of reduction in fluid volume. Other causes of volume depletion such as vomiting or diarrhea, may also lead to a fall in blood pressure; patients should be advised to consult with their physician.
Generally, it is recommended that dehydration, hypovolaemia or salt depletion be corrected before initiating treatment (in patients with heart failure, however, such corrective action must be carefully weighed against the risk of volume overload). When these conditions have become clinically relevant, treatment with ramipril must only be started or continued if appropriate steps are taken concurrently to prevent an excessive fall in blood pressure and deterioration of renal function.
In patients with ischemic heart disease or cerebrovascular disease, an excessive fall in blood pressure (BP) could result in a myocardial infarction or cerebrovascular accident (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions, Cardiac disorders). Because of the potential fall in BP in these patients, therapy with pms-RAMIPRIL-HCTZ should be started under close medical supervision. Such patients should be followed closely for the first weeks of treatment and whenever the dose of pms-RAMIPRIL-HCTZ is increased. In patients with severe congestive heart failure, with or without associated renal insufficiency, ACE inhibitor therapy may cause excessive hypotension and has been associated with oliguria, and/or progressive azotemia, and rarely, with acute renal failure and/or death.
If hypotension occurs, the patient should be placed in a supine position and, if necessary, receive an intravenous infusion of 0.9% sodium chloride. A transient hypotensive response may not be a contraindication to further doses which usually can be given without difficulty once BP has increased after volume expansion in hypertensive patients. However, lower doses of pms-RAMIPRIL-HCTZ should be considered. In patients receiving treatment following acute myocardial infarction, consideration should be given to discontinuation of pms-RAMIPRIL-HCTZ (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions, Cardiac disorders).
pms-RAMIPRIL-HCTZ may lower the state of patient alertness and/or reactivity, particularly at the start of treatment. Patients should be cautioned to report light-headedness, especially during the first few days of pms-RAMIPRIL-HCTZ therapy. If actual syncope occurs, the patients should be told to discontinue the drug and consult with their physician.
Hematologic
Neutropenia/Agranulocytosis
Agranulocytosis and bone marrow depression have been caused by ACE inhibitors. Several cases of agranulocytosis, neutropenia or leukopenia have been reported in which a causal relationship to ramipril cannot be excluded (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions). Current experience with the drug shows the incidence to be rare.
Hematological reactions to ACE inhibitors are more likely to occur in patients with impaired renal function and in those with concomitant collagen disease (e.g., lupus erythematosus or scleroderma) or in those treated with other drugs that may cause changes of the blood picture. Periodic monitoring of white blood cell counts should be considered (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, Hematological Monitoring).
Patients should be told to report promptly to their physician any indication of infection (e.g., sore throat, fever) as this may be a sign of neutropenia (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Hepatic/Biliary
Hepatitis (hepatocellular and/or cholestatic), elevations of liver enzymes and/or serum bilirubin have occurred during therapy with ACE inhibitors in patients with or without pre-existing liver abnormalities (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions). In most cases the changes were reversed on discontinuation of the drug. Should the patient receiving pms-RAMIPRIL-HCTZ experience any unexplained symptoms particularly during the first weeks or months of treatment, it is recommended that a full set of liver function tests and any other necessary investigations be carried out. Discontinuation of pms-RAMIPRIL-HCTZ should be considered when appropriate.
Rarely, ACE inhibitors, including ramipril, have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis and (sometimes) death. The mechanism of this syndrome is not understood. Patients receiving ACE inhibitors who develop jaundice or marked elevations of hepatic enzymes should discontinue the ACE inhibitor and receive appropriate medical follow-up.
Patients should be advised to return to their physician if they experience any symptoms possibly related to liver dysfunction. This would include "viral-like symptoms" in the first weeks to months of therapy (such as fever, malaise, muscle pain, rash or adenopathy which are possible indicators of hypersensitivity reactions), or if abdominal pain, nausea or vomiting, loss of appetite, jaundice, itching or any other unexplained symptoms occur during therapy (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Thiazides should be used with caution in patients with mild to moderate impairment of hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. pms-RAMIPRIL-HCTZ should not be used in patients with severe impairment of hepatic function (see CONTRAINDICATIONS).
There are no adequate studies in patients with cirrhosis and/or liver dysfunction. In patients with impaired liver function, response to the treatment with ramipril may be either increased or reduced. In addition, in patients in whom severe liver cirrhosis with oedema and ascites is present, the RAS may be significantly activated. pms-RAMIPRIL-HCTZ should be used with particular caution in patients with pre-existing liver abnormalities. In such patients, baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations and Conditions, Hepatic Insufficiency).
Immune
Angioedema – Head and Neck
Angioedema has been reported in patients treated with ACE inhibitors including ramipril. Life threatening angioedema has been reported in patients treated with ACE inhibitors including ramipril. The overall incidence is approximately 0.1 – 0.2%. Angioedema involving the face, extremities, lips, tongue, glottis and/or larynx has been reported in patients treated with ACE inhibitors. Angioedema associated with laryngeal involvement may be fatal. If laryngeal stridor or angioedema of the face, extremities, lips, tongue, or glottis occurs, pms-RAMIPRIL-HCTZ should be discontinued immediately, the patient treated appropriately in accordance with accepted medical care, and carefully observed until the swelling disappears. In instances where swelling is confined to the face and lips, the condition generally resolves without treatment, although antihistamines may be useful in relieving symptoms. Where there is involvement of tongue, glottis, or larynx, likely to cause airway obstruction, appropriate therapy (including, but not limited to 0.3 - 0.5 mL of subcutaneous epinephrine solution 1:1,000) should be administered promptly.
Angioedema, including laryngeal edema, may occur especially following the first dose of pms-RAMIPRIL-HCTZ. Patients should be so advised and told to report immediately any signs or symptoms suggesting angioedema, such as swelling of face, extremities, eyes, lips, tongue, difficulty in swallowing or breathing. They should immediately stop taking pms-RAMIPRIL-HCTZ and consult with their physician.
An increased incidence of angioedema was observed in patients taking ACE inhibitors and mTOR inhibitors (mammalian target of rapamycin inhibitors) (see DRUG INTERACTIONS).
Concomitant Use of mTOR Inhibitors, DPP-IV Inhibitors and NEP Inhibitors
Patients taking a concomitant mTOR inhibitor (e.g., sirolimus, everolimus, temsirolimus), DPP-IV inhibitor (e.g., sitagliptin) or neutral endopeptidase (NEP) inhibitor may be at increased risk for angioedema. Caution should be used when initiating ACE inhibitor therapy in patients already taking a mTOR, DPP-IV or NEP inhibitor or vice versa (see DRUG INTERACTIONS).
Concomitant Use of Sacubitril/Valsartan
A potential increased risk of angioedema has been reported with concomitant use of sacubitril/valsartan and ACE inhibitors (see CONTRAINDICATIONS).
Angioedema - Intestinal
Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases, facial angioedema also occurred. The intestinal angioedema symptoms resolved after stopping the ACE inhibitor (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions, Immune).
The incidence of angioedema during ACE inhibitor therapy has been reported to be higher in black than in non-black patients.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see CONTRAINDICATIONS).
Anaphylactoid Reactions to ACE Inhibitors During Membrane Exposure
Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes [e.g., polyacrylonitrile (PAN)] and treated concomitantly with an ACE inhibitor. Therefore, the use of pms-RAMIPRIL-HCTZ in patients dialyzed with high-flux membranes is contraindicated (see CONTRAINDICATIONS). Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. If such treatment is required, a different type of dialysis membrane or a different class of antihypertensive is recommended.
Anaphylactoid Reactions to ACE Inhibitors During LDL Apheresis
Rarely, patients receiving ACE inhibitors during low density lipoprotein apheresis with dextran sulfate have experienced life-threatening anaphylactoid reactions. These reactions were avoided by temporarily withholding the ACE inhibitor therapy prior to each apheresis. Therefore, the use of pms-RAMIPRIL-HCTZ in patients receiving low density lipoprotein apheresis with dextran sulfate is contraindicated (see CONTRAINDICATIONS). If such treatment is required, consideration should be given to using a different type of apheresis or a different class of antihypertensive agents.
Anaphylactoid Reactions to ACE Inhibitors During Desensitization
There have been isolated reports of patients experiencing sustained life threatening anaphylactoid reactions while receiving ACE inhibitors during desensitization treatment with hymenoptera (e.g., bees, wasps) venoma. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for ≥ 24 hours, but they have reappeared upon inadvertent rechallenge.
Hypersensitivity to Thiazide Diuretics
Sensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma.
The possibility of exacerbation or activation of systemic lupus erythematosus has been reported in patients treated with hydrochlorothiazide.
Nitritoid Reactions – Gold
Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including ramipril/hydrochlorothiazide (see DRUG INTERACTIONS).
Metabolism
Thiazides, including hydrochlorothiazide, can cause fluid or electrolyte imbalance (hypokalemia, hyponatremia, and hypochloremic alkalosis).
Hyperuricemia may occur, or acute gout may be precipitated, in certain patients receiving thiazide therapy.
Thiazides may decrease serum PBI (protein-bound iodine) levels without signs of thyroid disturbance.
Thiazides have been shown to increase excretion of magnesium; this may result in hypomagnesemia.
Thiazides may decrease urinary calcium excretion. Thiazides may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may be evidence of hidden hyperparathyroidism. Thiazides should be discontinued before carrying out tests of parathyroid function.
Increases in cholesterol, triglyceride and glucose levels may be associated with thiazide diuretic therapy.
Dosage adjustments of insulin or oral hypoglycemic agents may be required. Latent diabetes mellitus may become manifest during thiazide therapy.
Administration of ACE inhibitors in patients with diabetes may potentiate the blood glucose lowering effect of oral hypoglycemic agents or insulin (see DRUG INTERACTIONS, Drug-Drug Interactions).
Elevated serum potassium (> 5.7 mEq/L) was observed in approximately 1% of hypertensive patients in clinical trials treated with the ACE inhibitor ramipril. In most cases these were isolated values which resolved despite continued therapy. Hyperkalemia was not a cause of discontinuation of therapy in any hypertensive patient. Risk factors for the development of hyperkalemia may include renal insufficiency, diabetes mellitus, and the concomitant use of agents to treat hypokalemia or other drugs associated with increases in serum potassium (see DRUG INTERACTIONS, Drug-Drug Interactions, Agents Increasing Serum Potassium).
Patients should be told not to use salt substitutes containing potassium, potassium supplements or potassium sparing diuretics without consulting their physician.
Ophthalmologic
Acute Myopia and Secondary Angle-Closure Glaucoma
Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulphonamide or penicillin allergy.
Peri-Operative Considerations
Surgery/Anesthesia
In patients undergoing surgery or anesthesia with agents producing hypotension, pms-RAMIPRIL-HCTZ may block angiotensin II formation secondary to compensatory renin release. If hypotension occurs and is considered to be due to this mechanism, it may be corrected by volume repletion.
Thiazides may increase the responsiveness to tubocurarine.
Patients planning to undergo surgery and/or anesthesia should be told to inform their physician that they are taking an ACE inhibitor.
Renal
Renal Impairment
As a consequence of inhibiting the renin-angiotensin-aldosterone system (RAAS), changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the RAAS, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk; therefore, use of pms-RAMIPRIL-HCTZ should include appropriate assessment of renal function.
The use of ACE inhibitors – including the ramipril component of pms-RAMIPRIL-HCTZ – or ARBs with aliskiren-containing drugs is contraindicated in patients with diabetes mellitus (type 1 or 2), moderate to severe renal impairment (GFR < 60 mL/min/1.73m2), hyperkalemia (> 5 mMol/L) or congestive heart failure who are hypotensive (see CONTRAINDICATIONS; and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System [RAS]).
Concomitant use of ACE inhibitors – including the ramipril component of pms-RAMIPRIL-HCTZ, with ARBs is contraindicated in patients with diabetes with end organ damage due to risk of hyperkalemia, moderate to severe kidney insufficiency (GFR < 60 mL/min/1.73m2), hyperkalemia (> 5 mMol/L) or congestive heart failure who are hypotensive (see CONTRAINDICATIONS; and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System [RAS]).
pms-RAMIPRIL-HCTZ should be used with caution in patients with renal insufficiency as they may require reduced or less frequent doses (see DOSAGE AND ADMINISTRATION). Close monitoring of renal function during therapy should be performed as deemed appropriate in patients with renal insufficiency (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, Renal Function Monitoring).
Thiazides may not be appropriate diuretics for use in patients with renal impairment and are ineffective at GFR values ≤30 mL/min per 1.73 m2 body surface area (i.e., severe insufficiency). Azotemia may be precipitated or increased by hydrochlorothiazide. Cumulative effects of the drug may develop in patients with impaired renal function. If increasing azotemia and oliguria occur during treatment of severe progressive renal disease the diuretic should be discontinued.
Special Populations
Pregnant Women
ACE inhibitors can cause fetal and neonatal morbidity and mortality when administered to pregnant women. Several dozen cases have been reported in the world literature. When pregnancy is detected, pms-RAMIPRIL-HCTZ should be discontinued as soon as possible, and, if appropriate, alternative therapy should be started. Patients planning pregnancy should be changed to alternative antihypertensive treatments which have an established safety profile for use in pregnancy.
The use of ACE inhibitors is contraindicated during pregnancy.
Prematurity, patent ductus arteriosus, and other structural cardiac malformations, as well as neurologic malformations, have also been reported following exposure in the first trimester of pregnancy.
The use of ACE inhibitors during the second and third trimesters of pregnancy has been associated with fetal and neonatal injury including hypotension, neonatal skull hypoplasia, anuria, reversible or irreversible renal failure, and death. Oligohydramnios has also been reported, presumably resulting from decreased fetal renal function; oligohydramnios in this setting has been associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward
support of BP and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit. It is not known if ramipril or ramiprilat can be removed from the body by hemodialysis.
Since the use of pms-RAMIPRIL-HCTZ during pregnancy can cause injury and even death of the developing fetus, patients should be advised to report promptly to their physician if they become pregnant.
Animal Data
No teratogenic effects of ramipril were seen in studies of pregnant rats, rabbits, and cynomolgus monkeys at doses 2500x, 6.25x and 1,250x, respectively, the maximum human dose. In rats, the highest dose (1,000 mg/kg) caused reduced food intake in the dams, with consequent reduced birth weights of the pups and weight development during the lactation period. In rabbits, maternal effects were mortalities (≥ 100 mg/kg) and reduced body weight. In monkeys, maternal effects were mortalities (≥ 50 mg/kg), vomiting, and reduced weight gain.
Nursing Women
The presence of concentrations of ACE inhibitor and thiazides has been reported in human milk. The use of pms-RAMIPRIL-HCTZ is contraindicated during breastfeeding.
Pediatrics (< 18 years of age)
The safety and effectiveness of ramipril and hydrochlorothiazide (tablets) in children have not been established. Therefore, pms-RAMIPRIL-HCTZ is not indicated in this patient population.
Geriatrics (> 65 years of age)
Because of decreased cardiovascular reserve, greater sensitivity in older patients (> 65 years) may be expected. Evaluation of renal function at beginning of treatment is recommended.
Monitoring and Laboratory Tests
Hematology Monitoring
It is recommended that the white blood cell count be monitored to permit detection of a possible leukopenia due to the ACE inhibitor component of pms-RAMIPRIL-HCTZ, ramipril. More frequent monitoring is advised in the initial phase of treatment and in patients:
- with impaired renal function,
- those with concomitant collagen disease (e.g., lupus erythematosus or scleroderma) or
those treated with other drugs that can cause changes in the blood picture (see WARNINGS
AND PRECAUTIONS, Hematologic, Neutropenia/Agranulocytosis; and DRUG INTERACTIONS, Drug-Drug Interactions, Allopurinol, Immunosuppressants, Corticosteroids, Procainamide, Cytostatics and other substances that may change the blood picture).
Metabolism Monitoring
Appropriate monitoring of electrolytes and blood sugar is required.
It is recommended that serum sodium, potassium, calcium, uric acid and blood glucose be monitored regularly. More frequent monitoring of serum potassium is necessary in patients with impaired renal function.
Renal Function Monitoring
Use of pms-RAMIPRIL-HCTZ should include appropriate assessment of renal function, particularly in the initial weeks of treatment.
Particularly careful monitoring is required in patients with:
- heart failure
- renovascular disease (atherosclerotic renal artery stenosis (AS-RAS) and fibromuscular dysplasia (FMD))
- impairment of renal function
- kidney transplant
- elderly patients
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most frequent adverse drug reactions observed with ramipril and hydrochlorothiazide tablets were: headache (3.9%), dizziness (2.2%) and bronchitis (2.1%). The common serious adverse event (AE) pooled from the different clinical trials was tachycardia (0.2%).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions, the adverse drug reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 1 – Adverse Events Occurring ≥ 1% in Patients Taking Ramipril and Hydrochlorothiazide in
Controlled Clinical Trials
Adverse Events
Ramipril + Hydrochlorothiazide* n=967 (%) | Ramipril n=1,058 (%) | Hydrochlorothiazide n=515 (%) | Placebo n=44 (%) | |
| Headache | 3.9 | 1.7 | 6.0 | 4.5 |
| Dizziness | 2.2 | 1.5 | 1.0 | 4.5 |
| Bronchitis | 2.1 | 0.5 | 0.4 | 0.0 |
| Neuralgia | 1.9 | 0.4 | 0.4 | 2.3 |
| Infection | 1.8 | 0.4 | 1.2 | 2.3 |
| Upper respiratory infection | 1.4 | 0.4 | 0.8 | 2.3 |
| Asthenia | 1.3 | 1.3 | 1.6 | 2.3 |
| Cough increased | 1.3 | 1.2 | 1.0 | 0.0 |
| Back pain | 1.0 | 0.6 | 0.6 | 0.0 |
*: Patients taking ramipril and hydrochlorothiazide tablets or ramipril + hydrochlorothiazide in combination.
Less Common Clinical Trial Adverse Drug Reactions (< 1%)
Cardiac disorders: angina pectoris, palpitation, peripheral edema, tachycardia.
Ear and labyrinth disorders: hearing loss, tinnitus.
Eye disorders: conjunctivitis, visual disturbances (including blurred vision).
Gastrointestinal disorders: abdominal pain (sometimes with enzyme changes suggesting pancreatitis), aphthous stomatitis, constipation, dry mouth, dyspepsia, dysphagia, gastroenteritis, gastritis, gastrointestinal pain, gingivitis, increased salivation, nausea, upper abdominal pain.
General disorders and administration site conditions: chest pain, fever, shock.
Hepatobiliary disorders: increased hepatic enzymes and/or conjugated bilirubin, cholestatic or cytolytic hepatitis. Calculous cholecystitis (due to hydrochlorothiazide).
Immune system disorders: allergic reactions.
Metabolism and nutrition disorders: anorexia, decreased appetite, excessive thirst, gout, hyperglycemia, hyperuricemia, hypokalemia, weight gain (related to ramipril).
Musculoskeletal and connective tissue disorders: arthralgia, arthritis, myalgia.
Nervous system disorders: burning sensation (mainly to the skin of face or extremities), disorders of balance, neuropathy, paresthesia, polyneuritis, taste loss, tremor, vertigo.
Psychiatric disorders: anxiety, apathy, depression, insomnia, nervousness, sleep disorder, somnolence.
Renal and urinary disorders: abnormal kidney function, increase in urinary output (in connection with an improvement in cardiac performance), renal failure.
Reproductive system and breast disorders: impotence.
Respiratory, thoracic and mediastinal disorders: dyspnea, sinusitis.
Skin and subcutaneous tissue disorders: alopecia, angioedema, erythroderma, maculopapular rash, maculopapular exanthema, pruritus, psoriasis, purpura, rash, sweating.
Vascular disorders: hot flushes, hypotension, postural hypotension, syncope.
Abnormal Hematologic and Clinical Chemistry Findings
Hematologic: decrease in red blood cell count, hemoglobin or hematocrit, leucocytosis.
Hydrochlorothiazide
Renal function test: increased serum concentrations of uric acid.
Cholesterol: increase in serum cholesterol and triglycerides.
Glucose: lower tolerance to glucose. In patients with diabetes mellitus, this may lead to a deterioration of the metabolic control.
Post-Market Adverse Drug Reactions
Blood and lymphatic system disorders: Agranulocytosis, bone marrow depression, eosinophilia, hemolytic anemia, reduction in the white blood cell or blood platelet count, neutropenia, pancytopenia. Hemoconcentration in the context of fluid depletion (see WARNINGS AND PRECAUTIONS, Hematologic; and DRUG INTERACTIONS).
Cardiac disorders: angina pectoris, cardiac arrhythmias, myocardial infarction, myocardial ischemia, palpitations, peripheral oedema, tachycardia.
Endocrine disorders: Syndrome of inappropriate antidiuretic hormone secretion (SIADH).
Ear and labyrinth disorders: disturbed hearing, tinnitus.
Eye disorders: decreased lacrimation, visual disturbances, xanthopsia due to hydrochlorothiazide.
Gastrointestinal disorders: abdominal discomfort, constipation, diarrhea, digestive disturbances, dryness of the mouth, gastric pain (including gastritis-like gastric pain), glossitis, inflammatory reactions of the oral cavity and gastrointestinal tract, diarrhea, increased levels of
pancreatic enzymes, intestinal angioedema, nausea, pancreatitis (cases of fatal outcome have been very exceptionally reported), vomiting. Sialadenitis due to hydrochlorothiazide.
General disorders and administration site conditions: asthenia, fatigue, fever, weakness.
Hepatobiliary disorders: cholestatic jaundice, hepatocellular damage, increases in serum levels of hepatic enzymes and/or bilirubin, liver damage (including acute liver failure).
Immune system disorders: anaphylactic or anaphylactoid reactions to ramipril or any of the other ingredients are rare (see WARNINGS AND PRECAUTIONS, Immune). Anaphylactic reactions to hydrochlorothiazide are possible. The likelihood and the severity of anaphylactoid reactions to insect venoma are increased under ACE inhibition. Increased antinuclear antibodies.
Metabolism and nutrition disorders: decline in serum sodium concentration; decrease in potassium concentration due to hydrochlorothiazide, dehydration, development or aggravation of a metabolic alkalosis, glycosuria (due to hydrochlorothiazide); hypochloremia, hypomagnesemia, hypercalcemia, increase in the concentration of serum potassium due to ramipril. General signs of disturbances in the electrolyte balance: confusion, drowsiness, headache, increased fluid excretion and muscle cramps.
Musculoskeletal and connective tissue disorders: arthralgia, muscle cramps, myalgia. Muscular weakness, musculoskeletal stiffness, tetany due to hydrochlorothiazide.
Nervous system disorders: cerebral ischaemia (including ischaemic stroke and transient ischaemic attack), disorders of balance, dizziness, headache, impaired psychomotor skills (impaired reactions), light-headedness, paresthesia, smell, taste disturbances and tremor.
Psychiatric disorders: attention disturbances, confusion, depressed mood, feeling of anxiety, nervousness, restlessness, somnolence.
Renal and urinary disorders: increase in serum urea and serum creatinine and impairment of renal function, progression to acute renal failure, interstitial nephritis and pre-existing proteinuria may deteriorate (though ACE inhibitors usually reduce proteinuria).
Respiratory, thoracic and mediastinal disorders: bronchitis, bronchospasm (including aggravated asthma), dry (non-productive) tickling cough, dyspnea, nasal congestion, sinusitis. Alveolitis allergic (pneumonitis), non-cardiogenic pulmonary oedema due to hydrochlorothiazide.
Reproductive system and breast disorders: gynaecomastia, reduced libido, transient erectile impotence.
Skin and subcutaneous tissue disorders: alopecia, cutaneous or mucosal reactions such as rash, pruritus or urticaria, erythema multiforme, exacerbation of psoriasis, exfoliative dermatitis, maculopapular rash, pemphigoid or lichenoid exanthema or enanthema, pemphigus,
photosensitivity, psoriasiform, Stevens-Johnson syndrome, sweating, systemic lupus erythematosus, toxic epidermal necrolysis.
Angioedema. Very exceptionally, the airway obstruction resulting from angioedema may have a fatal outcome.
Vascular disorders: disturbed orthostatic regulation, exacerbation of perfusion disturbances due to vascular stenosis, hypotension, precipitation or intensification of Raynaud’s phenomenon, syncope, thrombosis (in the context of severe fluid depletion), vascular stenosis, vasculitis.
DRUG INTERACTIONS
Overview
Drug-Drug Interactions
Table 2 - Established or Potential Drug-Drug Interactions
| Proper Name | Ref | Effect | Clinical Comment |
| Sacubitril/Valsartan | T | The concomitant use of an ACE inhibitor with sacubitril/valsartan is contraindicated, as the concomitant inhibition of Neprilysin and ACE increases the risk of angioedema. | Concomitant use with sacubitril/valsartan is contraindicated. Do not initiate ramipril until 36 hours after the last dose of sacubitril/valsartan. In the case of a switch from ramipril to sacubitril/valsartan, do not start sacubitril/valsartan until 36 hours after the last dose of ramipril (see CONTRAINDICATIONS; and DOSAGE AND ADMINISTRATION). |
| Acenocoumarol | CT | No significant change in blood pressure, thrombotest time and coagulation factors with ramipril. | In a multi-dose double-blind, placebo-controlled, pharmacodynamic interaction study with 14 patients with mild hypertension administered both ramipril and therapeutic doses of acenocoumarol, blood pressure, thrombotest time and coagulation factors were not significantly changed. |
| Agents Causing Renin Release | T | Antihypertensive effect augmented. | The antihypertensive effect of ramipril is augmented by antihypertensive agents that cause renin release. |
| Agents Increasing Serum Potassium | CT | Since ramipril decreases aldosterone production, sometimes severe elevation of serum potassium may occur. | Potassium sparing diuretics such as spironolactone, triamterene or amiloride, potassium supplements, or other medicinal products that may increase kalemia should be given only for documented hypokalemia. Use with caution, including salt substitutes which contain potassium. Monitor serum potassium frequently. |
| Alcohol, Barbiturates, or Narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates and narcotics especially with initiation of therapy. |
| Proper Name | Ref | Effect | Clinical Comment |
Allopurinol, Immuno-Suppressants, Corticosteroids, Procainamide, Cytostatics and Other Substances that may Change the Blood Picture | T | Increased likelihood of hematological reactions. | |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics. | Monitor serum potassium level. |
| Antacids | CT | In one open-label, randomized, cross-over single dose study in 24 male subjects, it was determined that the bioavailability of ramipril and the pharmacokinetic profile of ramiprilat were not affected by concomitant administration of the antacid, magnesium and aluminum hydroxides. | No effect |
Antidiabetic Agents (e.g., insulin and oral hypoglycemic) | CT | Hypoglycemic reactions with ACE inhibitors Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | ACE inhibitors drugs may reduce insulin resistance. In isolated cases, such reduction may lead to hypoglycaemic reactions in patients concomitantly treated with antidiabetics. Therefore, monitor closely blood glucose particularly in the initial phase of coadministration. Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive Drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g., guanethidine, methyldopa, beta-blockers, vasodilators, calcium channel blockers, ACE inhibitors, ARBs, and direct renin inhibitors). | |
Antineoplastic Drugs, Including Cyclophosphamide and Methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. Increased hematological reactions may result from a combined effect of a cytotoxic agent and ACE inhibitor. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Proper Name | Ref | Effect | Clinical Comment |
| Bile Acid Sequestrants (e.g., cholestyramine) | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothiazide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
| Calcium and Vitamin D Supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Carbenoxolone, Large Amounts of Liquorice, Laxatives (in case of a prolonged use), and Other Kaliuretic Agents | T | Hypokalemia | Monitor potassium levels. |
| Concomitant Diuretic Therapy | CT | Hypotensive effects | To minimize the possibility of hypotensive effects after the 1st dose of ramipril, discontinue the diuretic or increase the salt intake prior to initiation of treatment with ramipril. If it is not possible to discontinue the diuretic, the starting dose of ramipril should be reduced. The patient should be closely observed for several hours following the initial dose and until blood pressure has stabilized (see WARNINGS AND PRECAUTIONS; and DOSAGE AND ADMINISTRATION). |
| Corticosteroids, and Adrenocorticotropic Hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium levels and adjust medications, as required. |
| Desensitization therapy | The likelihood and severity of anaphylactic and anaphylactoid reactions to insect venoma is increased under ACE inhibition. | It is assumed that this effect may also occur in connection with other allergens. | |
| Digoxin | CT | In one open-label study in 12 subjects, administered multiple doses of both ramipril and digoxin, no changes were found in serum levels of ramipril, ramiprilat, and digoxin. Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. |
| Proper Name | Ref | Effect | Clinical Comment |
| DDP-IV Inhibitors (linagliptin, saxagliptin, sitagliptin) | Patients taking concomitant DDP-IV inhibitor therapy may be at increased risk for angioedema. | Caution should be used when initiating pms-RAMIPRIL-HCTZ in patients already taking a DPP-IV inhibitor or vice versa (see WARNINGS AND PRECAUTIONS, Immune, Angioedema - Head and Neck). | |
Drugs That Alter GI Motility, i.e., anticholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
| Dual Blockade of the Renin-Angiotensin System (RAS) | CT, C | Dual Blockade of the Renin-Angiotensin System (RAS) with ACE inhibitors, including the ramipril component of pms-RAMIPRIL-HCTZ, ARBs or aliskiren-containing drugs are contraindicated in patients with diabetes and/or moderate to severe renal impairment. The use of ACE inhibitors, including the ramipril component of pms-RAMIPRIL-HCTZ, in combination with an ARB is contraindicated in patients with diabetic nephropathy. Further, coadministration of ACE inhibitors, including the ramipril component of pms-RAMIPRIL-HCTZ, with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia. | See CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin- Angiotensin System (RAS). |
| Gold | CS | Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including ramipril. |
| Proper Name | Ref | Effect | Clinical Comment |
Gout Medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RC S | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The coadministration hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dose adjustment of gout medications may be required. |
| Heparin | T | Rise in serum potassium concentration possible. | |
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving ACE inhibitors during therapy with lithium. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If these drugs must be used together, decrease lithium dose by 50% with close monitoring of lithium concentration, serum electrolytes and fluid intake. If a diuretic is also used, the risk of lithium toxicity may be further increased. |
| Methyldopa | T | Hemolysis possible | |
| Neprilysin (NEP) Inhibitors | T | ACE inhibitors are known to cause angioedema. This risk may be elevated when used concomitantly with a neutral endopeptidase inhibitor. | Caution should be used when initiating pms-RAMIPRIL-HCTZ in patients already taking a neutral endopeptidase inhibitor or vice versa (see WARNINGS AND PRECAUTIONS, Immune, Angioedema - Head and Neck). |
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) and Acetylsalicylic Acid | CT | The antihypertensive effects of ACE inhibitors may be reduced with concomitant administration of NSAIDs (e.g., indomethacin). Concomitant treatment of ACE inhibitors and NSAIDs may lead to an increased risk of worsening renal function and an increase in serum potassium. NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along with thiazide-induced decreases in glomerular filtration rate (GFR) may lead to acute renal failure. Patients with heart failure may be at particular risk. | Avoid if possible. If not possible, close monitoring of serum creatinine, potassium and patient’s weight is recommended. Observe the patient to ensure diuretic effects are obtained. Monitor blood pressure and renal function. Increase dose if necessary or discontinue NSAID. |
| Other Substances with Antihypertensive Potential (e.g., nitrates) | T | Potentiation of the antihypertensive effect is to be anticipated. |
| Proper Name | Ref | Effect | Clinical Comment |
| Salt | T | Possible attenuation of the antihypertensive effect by increased dietary salt intake. | |
Selective Serotonin Reuptake Inhibitors (SSRIs, e.g., citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
Skeletal Muscle Relaxants of the Curare Family, e.g., tubocurare | C | Thiazide drugs may increase the responsiveness of skeletal muscle relaxants, such as curare derivatives. Thiazides may enhance the effects of nondepolarizing skeletal muscle relaxants potentially leading to prolonged respiratory depression. Thiazide-induced hypokalemia increases resistance to depolarization by hyperpolarizing the end plate resulting in enhanced myoneural blockade. | Monitor and correct thiazide-induced hypokalemia. Consider decreasing dose of nondepolarizing skeletal muscle relaxant if hypokalemia cannot be corrected before administration of muscle relaxants is required. |
| Sympathomimetics | T | Reduce the antihypertensive effect. May decrease arterial responsiveness to norepinephrine but this diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use. | Clinical significance is unknown. Particularly close blood pressure monitoring is recommended. |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate supplements, or adjust topiramate dose as necessary. |
mTOR Inhibitors (e.g., sirolimus, everolimus, temsirolimus) | C | An increased incidence of angioedema was observed in patients taking ACE inhibitors and mTOR inhibitors (mammalian target of rapamycin inhibitors). | Caution should be used when initiating pms-RAMIPRIL-HCTZ in patients already taking mTOR inhibitors or vice versa (see WARNINGS AND PRECAUTIONS, Angioedema - Head and Neck). |
| Warfarin | No alteration of the anticoagulant effects with ramipril. |
Legend: C= Case Study, RCS= Retrospective Cohort Study, CT= Clinical Trial; T = Theoretical
Drug-Food Interactions
No substantial drug-food interaction has been detected with ramipril or hydrochlorothiazide.
Drug-Laboratory Interactions
Tests for Parathyroid Function
Hydrochlorothiazide stimulates renal calcium reabsorption and may cause hypercalcemia. This must be considered when carrying out tests for parathyroid function.
Drug-Lifestyle Interactions
No information available.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Dosage should be individualized.
- pms-RAMIPRIL-HCTZ (ramipril/hydrochlorothiazide) is not for initial therapy.
- The dose of pms-RAMIPRIL-HCTZ should be determined by the titration of the individual components.
- Special attention for dialysis patients.
Recommended Dose and Dosage Adjustment
Once the patient has been successfully titrated with the individual components as described below, pms-RAMIPRIL-HCTZ may be substituted if the titrated dose and dosing schedule can be achieved by the fixed combination (see INDICATIONS AND CLINICAL USE; and WARNINGS AND PRECAUTIONS).
Usual dosage: 2.5 mg ramipril and 12.5 mg hydrochlorothiazide (corresponding to 1 tablet pms-RAMIPRIL-HCTZ 2.5/12.5) daily. Generally, it is recommended that the daily dose be administered in the morning as a single dose.
Due to the risk of angioedema when used concomitantly with sacubitril/valsartan, pms-RAMIPRIL-HCTZ must not be started until 36 hours has passed following the last dose of sacubitril/valsartan (see CONTRAINDICATIONS).
Titration will be based on physician’s judgment according to severity of hypertension and other associated risk factors.
Maximum daily dose: 10 mg ramipril and 50 mg hydrochlorothiazide (corresponding to 4 tablets pms-RAMIPRIL-HCTZ 2.5/12.5 or 2 tablets pms-RAMIPRIL-HCTZ 5/25).
Dosage in Elderly Patients
Initial doses should be lower and subsequent dose titration should be more gradual because of greater chance of undesirable effects especially in very old and frail patients (see WARNINGS AND PRECAUTIONS).
Dosage in Patients with Impaired Renal Function
Moderate renal impairment (creatinine clearance 30 - 60 mL/min/1.73 m2): In patients with moderate renal impairment, treatment is started with ramipril alone at a daily dose of 1.25 mg. After gradually increasing the dose of ramipril, medication with the combination preparation is started at a daily dose of 2.5 mg ramipril /12.5 mg hydrochlorothiazide. Maximum permitted
daily dose: 5 mg ramipril/25 mg hydrochlorothiazide. pms-RAMIPRIL-HCTZ 10 mg/12.5 mg and pms-RAMIPRIL-HCTZ 10 mg/25 mg MUST NOT be used in these patients.
pms-RAMIPRIL-HCTZ is contraindicated in patients with severe renal impairment (creatinine clearance < 30 mL/min/1.73 m2) and in dialysis patients (see CONTRAINDICATIONS).
Dosage in Patients with Impaired Hepatic Function
Mild or moderate hepatic impairment: In patients with mild to moderate hepatic impairment, treatment with pms-RAMIPRIL-HCTZ must be initiated only under close medical supervision and the maximum daily dose is 2.5 mg of ramipril/12.5 mg hydrochlorothiazide. pms-RAMIPRIL-HCTZ 5 mg/12.5 mg, 5 mg/25 mg, 10 mg/12.5 mg and 10 mg/25 mg MUST NOT be used in these patients.
pms-RAMIPRIL-HCTZ is contraindicated in patients with severe hepatic impairment (see CONTRAINDICATIONS).
Dosing in Patients Pre-Treated with Diuretics
In patients pre-treated with a diuretic, consideration must be given to discontinuing the diuretic ≥ 2 - 3 days (depending on the duration of action of the diuretic) before starting treatment with pms-RAMIPRIL-HCTZ or at least to reducing the diuretic dose. Should discontinuation not be possible, it is recommended that treatment be initiated with the smallest possible dosage of ramipril (1.25 mg daily) in a free combination. It is recommended that, subsequently, a changeover be made to an initial daily dose of ≤ 2.5 mg ramipril /12.5 mg hydrochlorothiazide.
Missed Dose
If a dose of this medication has been missed, it should be taken as soon as possible. However, if it is almost time for the next dose, skip the missed dose and go back to the regular dosing schedule. Do not double doses.
Administration
pms-RAMIPRIL-HCTZ tablets should be swallowed with sufficient amounts of liquid (approximately ½ glass). The tablets must not be chewed or crushed.
Generally, it is recommended that the daily dose be administered in the morning as a single dose. No substantial food effect is to be expected with pms-RAMIPRIL-HCTZ.
OVERDOSAGE
Overdosage may cause persistent diuresis, excessive peripheral vasodilatation (with marked hypotension, electrolyte disturbances, cardiac arrhythmias, impairment of consciousness up to and including coma and cerebral convulsions), bradycardia, renal failure, paresis and paralytic ileus.
In patients with obstruction of urinary outflow (e.g., from prostatic hyperplasia), sudden diuresis may induce acute urinary retention with overdistension of the bladder.
Management
Treatment is symptomatic and supportive. Primary detoxification by, for example, administration of adsorbents may be considered. In the event of hypotension, administration of α1-adrenergic agonists (e.g., norepinephrine, dopamine) or angiotensin II (angiotensinamide) must be considered in addition to volume and salt substitution.
In attempting to eliminate ramipril, or ramiprilat, there is limited/no experience available concerning the efficacy of forced diuresis, altering urine pH, hemofiltration or dialysis. If dialysis or hemofiltration is nevertheless contemplated, consider risks of anaphylactoid reactions with high flux membrane (see WARNINGS AND PRECAUTIONS, Immune, Anaphylactoid Reactions to ACE Inhibitors During Membrane Exposure).
Removal of thiazide diuretics by dialysis is negligible.
| For the management of a suspected drug overdose, contact your | ||
| regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ramipril and hydrochlorothiazide tablets have antihypertensive and diuretic effects. Ramipril and hydrochlorothiazide are used singly or together for antihypertensive therapy. The antihypertensive effects of both substances are complementary.
The blood-pressure-lowering effects of both components together are greater than the effect of either monotherapy. In patients treated with ramipril and a thiazide diuretic there was essentially no change in serum potassium (see WARNINGS AND PRECAUTIONS, Metabolism).
Pharmacodynamics
Ramipril
Administration of ramipril causes a marked reduction in peripheral arterial resistance. Administration of ramipril to patients with hypertension leads to a reduction in supine and standing blood pressure (BP) without a compensatory rise in heart rate.
In most patients the onset of the antihypertensive effect of a single dose becomes apparent 1 - 2 hours after oral administration. The peak effect of a single dose is usually reached 3 - 6 hours after oral administration. The antihypertensive effect of a single dose usually lasts for 24 hours.
Abrupt discontinuation of ramipril does not produce a rapid and excessive rebound increase in BP.
Hydrochlorothiazide
Electrolyte and water excretion starts approximately 2 hours after administration, reaches its peak after 3 - 6 hours and lasts from 6 - 12 hours.
The onset of the antihypertensive effect requires several days and administration for 2 - 4 weeks is necessary for optimal therapeutic effect.
Pharmacokinetics
Table 3 - Summary of Pharmacokinetic Parameters after Single Doses of 5/25 mg Ramipril/Hydrochlorothiazide Tablets, 5 mg Ramipril, 25 mg Hydrochlorothiazide or 5 mg Ramipril + 25 mg
Hydrochlorothiazide from Study HOE9829/1502
| Arithmetic Mean (CV %) (Geometric LS Mean) | ||||
| Substrate | Cmax (ng/mL) | Tmax (h) | AUCT (ng*h/mL) | AUC(0-72) (ng*h/mL) |
Ramipril/ hydrochlorothiazide 5/25 mg tablet | ||||
| 19.348±37.7 (17.896) | 0.50±26.8 | 25.256±63.3 (21.646) | --- |
| 6.576±47.4 (6.061) | 2.50±33.3 | --- | 119.102±25.3 (116.192) |
| 140.95±23.8 (137.08) | 2.00±44.2 | 993.53±18.5 (980.65) | --- |
| Ramipril 5 mg tablet | ||||
| 21.712±42.2 (19.649) | 0.50±70.0 | 26.546±70.9 (22.500) | --- |
| 6.588±62.7 (5.703) | 2.57±51.3 | --- | 116.693±29.0 (110.362) |
| Hydrochlorothiazide 25 mg | ||||
| tablet | ||||
| 140.52±24.2 (136.21) | 2.00±47.3 | 1,048.70±24.8 (1,021.52) | --- |
| 5 mg ramipril tablet + 25 mg hydrochlorothiazide tablet | ||||
| 21.035±33.1 (19.896) | 0.53±35.3 | 25.317±65.1 (22.024) | --- |
| 5.941 ± 51.6 (5.328) | 3.00±38.0 | --- | 108.716±21.1 (105.633) |
| 144.85±30.3 (138.38) | 2.00±36.5 | 969.92±21.5 (953.41 ) | --- |
No significant pharmacokinetic interaction has been observed between ramipril and hydrochlorothiazide administered as a fixed combination formulation of ramipril/hydrochlorothiazide tablets (ramipril/hydrochlorothiazide 5 mg/ 25 mg tablet Aventis
Pharma Canada Inc.) under fasting conditions, on the basis of ramipril and hydrochlorothiazide parameters (Cmax and AUC).
Ramipril
Absorption
Ramipril is rapidly absorbed after oral administration. As measured by the recovery of radioactivity in the urine, which represents only one of the elimination routes, absorption of ramipril is ≥ 56%. Administration of ramipril at the same time as food has no relevant effect on absorption.
Distribution
As a result of this activation/metabolization of the prodrug, approximately 20% of orally administered ramipril is bioavailable.
The bioavailability of ramiprilat after oral administration of 2.5 and 5 mg ramipril is approximately 45% compared with its availability after intravenous administration of the same doses.
Peak plasma concentrations of ramipril are reached within 1 hour after oral administration. Peak plasma concentrations of ramiprilat are reached 2 - 4 hours after oral administration of ramipril.
The protein-binding of ramipril and ramiprilat is approximately 73% and 56%, respectively.
Metabolism
The prodrug ramipril undergoes an extensive hepatic first pass metabolism (hydrolysis), which is essential for the formation of the sole active metabolite ramiprilat. In addition to this activation into ramiprilat, ramipril is glucuronized and transformed into ramipril diketopiperazine (ester). Ramiprilat is glucuronized as well and transformed into ramiprilat diketopiperazine (acid).
When high doses (10 mg) of ramipril are administered, impairment of hepatic function retards the activation of ramipril into ramiprilat, resulting in increased ramipril plasma levels.
Excretion
Following oral administration of 10 mg of radioactive labelled ramipril, approximately 40% of total radioactivity is excreted in faeces and approximately 60% in urine. The elimination half-life of ramipril is approximately 1 hour.
Approximately 80 - 90% of the metabolites in urine and bile have been identified as ramiprilat or ramiprilat metabolites. Ramipril glucuronide and ramipril diketopiperazine represented approximately 10 - 20% of the total amount, whereas unmetabolized ramipril accounted for approximately 2%.
Plasma concentrations of ramiprilat decline in a polyphasic manner. The initial distribution and elimination phase has a half-life of approximately 3 hours. It is followed by an intermediate
phase (half-life approximately 15 hours) and a terminal phase with very low plasma ramiprilat concentrations and a half-life of approximately 4 - 5 days.
Despite this long terminal phase, a single daily dose of 2.5 mg ramipril or more yields steady state plasma concentrations of ramiprilat after approximately 4 days. The "effective" half-life, which is relevant for dosage, is 13 - 17 hours under multiple-dose conditions.
Renal excretion of ramiprilat is reduced in patients with impaired renal function, and renal ramiprilat clearance is proportionally related to creatinine clearance. This results in elevated plasma concentrations of ramiprilat, which decrease more slowly than in persons with normal renal function (see WARNINGS AND PRECAUTIONS, Renal)
Hydrochlorothiazide
Absorption
The bioavailability of hydrochlorothiazide after oral administration is approximately 70%.
Distribution
Approximately 40% of hydrochlorothiazide is bound to plasma proteins.
Metabolism
Hydrochlorothiazide undergoes negligible hepatic metabolism and has not been shown to induce or inhibit any CYP450 isoenzymes.
Excretion
Hydrochlorothiazide is excreted almost entirely (>95%) by renal route in unchanged form. After oral administration of a single dose, 50 - 70% is excreted within 24 hours.
The elimination half-life is 5 - 6 hours. In renal insufficiency excretion is reduced and the half-life prolonged. Renal clearance of hydrochlorothiazide correlates closely with creatinine clearance.
Special Populations and Conditions
Geriatrics (> 65 years of age)
In healthy subjects aged 65 - 76 years, ramipril and ramiprilat kinetics are similar to those in healthy young subjects.
Race
The average response to ACE inhibitor monotherapy was lower in black hypertensive patients (usually a low-renin hypertensive population) than in non-black patients.
Cardiovascular Insufficiency
The clearance of hydrochlorothiazide may be decreased in patients with congestive heart failure.
Hepatic Insufficiency
No relevant changes in the pharmacokinetics of hydrochlorothiazide have been noted in liver cirrhosis.
In patients with impaired liver function, plasma ramipril levels increased about 3-fold, although peak concentrations of ramiprilat in these patients were not different from those seen in patients with normal hepatic function.
Hydrochlorothiazide should not be administered in hepatic coma or pre-coma. It should be used only with caution in patients with progressive hepatic disease (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary).
Renal Insufficiency
Renal excretion of ramipril, ramiprilat, and its metabolite is reduced in patients with impaired renal function, and renal ramiprilat clearance is proportionally related to creatinine clearance. This results in elevated plasma concentrations of ramiprilat, which decreases more slowly than in persons with normal renal function.
In patients with creatinine clearance < 40 mL/min/1.73m2, increases in Cmax and AUC of ramipril and ramiprilat compared to normal subjects were observed following multiple dosing with 5 mg ramipril (see DOSAGE AND ADMINISTRATION, Dosage in patients with impaired renal function).
The clearance of hydrochlorothiazide is decreased in renal failure.
Hydrochlorothiazide must be present at the site of action in the renal tubule in sufficient concentration in order to achieve its therapeutic effect. Hydrochlorothiazide reaches its site of action almost exclusively by secretion into the tubular fluid via the organic acid cotransporter. In mild renal insufficiency, higher doses are required to achieve sufficient concentrations of drug at the site of action due to decreased tubular secretion in renal failure. However, hydrochlorothiazide becomes ineffective once creatinine clearance < 30 - 50 mL/min.
STORAGE AND STABILITY
Store pms-RAMIPRIL-HCTZ (ramipril/hydrochlorothiazide) between 15°C - 25°C. Protect from heat and humidity.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Tablets
2.5 mg/12.5 mg: Each white to almost white, oblong, scored tablet with “RH” and “1A”
debossed on either side of the score on one side and nothing on the other scored side, contains 2.5 mg of Ramipril, 12.5 mg of Hydrochlorothiazide and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Lactose Monohydrate, Microcrystalline Cellulose, and Sodium Stearyl Fumarate. Available in HDPE bottles of 100 tablets.
5 mg/12.5 mg: Each pink, oblong, scored tablet with “RH” and “2A” debossed on either side of the score on one side and nothing on the other scored side contains 5 mg of Ramipril, 12.5 mg of Hydrochlorothiazide and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Lactose Monohydrate, Microcrystalline Cellulose, Sodium Stearyl Fumarate, and Red Iron Oxide. Available in HDPE bottles of 100 tablets and in blister packages of
30.
10 mg/12.5 mg: Each orange, oblong, scored tablet with “RH” and “3A” debossed on either side of the score on one side and nothing on the other scored side, contains 10 mg of Ramipril, 12.5 mg of Hydrochlorothiazide and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Microcrystalline Cellulose, Lactose Monohydrate, Sodium Stearyl Fumarate, Red Iron Oxide, and Yellow Iron Oxide. Available in HDPE bottles of 100 tablets and in blister packages of 30.
5 mg/25 mg: Each white to almost white, oblong, scored tablet with “RH” and “2V”
debossed on either side of the score on one side and nothing on the other scored side, contains 5 mg of Ramipril, 25 mg of Hydrochlorothiazide and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Lactose Monohydrate, Microcrystalline Cellulose, and Sodium Stearyl Fumarate. Available in HDPE bottles of 100 tablets.
10 mg/25 mg: Each pink, oblong, scored tablet with “RH” and “3V” debossed on either side of the score on one side and nothing on the other scored side contains 10 mg of Ramipril, 25 mg of Hydrochlorothiazide and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Crospovidone, Hypromellose, Lactose Monohydrate, Microcrystalline Cellulose, Sodium Stearyl Fumarate, and Red Iron Oxide. Available in HDPE bottles of 100 tablets and in blister packages of
30.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ramipril
Chemical name:
Company's Chemical name: 2-[N-[(S)-1-ethoxycarbonyl-3-phenylpropyl]-L-alanyl]-(1 S, 3S,
5S)-2-azabicyclo-[3.3.0] octane-3-carboxylic acid
USP Chemical name: Cyclopenta[b]pyrrole-2-carboxylic acid, 1-[2-[[1-(ethoxycarbonyl)-
3-phenylpropyl]amino]-1-oxopropyl]octahydro-, [2S-[1 [R*(R*)],2a, 3aß,6aß ]]-.(2S,3aS,6aS)-1-[(S)-N-[(S)-1-Carboxy-3-phenylpropyl] alanyl] octahydrocyclopenta [b]pyrrole-2 -carboxylic acid, 1-ethyl ester
Molecular formula: C23H32N2O5
Molecular mass: 416.52 g/mol
Structural formula:
CH2CH2C NH
COOC2H5
H
C
H
C
CH3
O
N H H
HOOC
Physicochemical properties: A white to off-white crystalline powder with a melting point of
105°C to 112°C. Slightly soluble in water, and freely soluble in ethanol and methanol.
Drug Substance
Proper name: Hydrochlorothiazide
Chemical name: 6-Chloro-3, 4-dihydro-2H-1, 2, 4-benzothiadiazine-7-sulfonamide
1, 1-dioxide
Molecular formula: C7H8ClN3O4S2
Molecular mass: 297.72 g/mol
Structural formula:
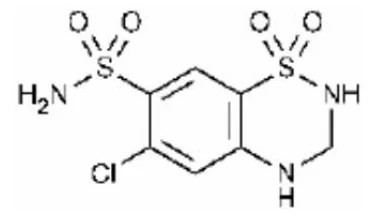
Physicochemical properties: A white or almost white crystalline powder, very slightly soluble in water, soluble in acetone, sparingly soluble in alcohol. It dissolves in dilute solutions of alkali hydroxides.
CLINICAL TRIALS
Comparative Bioavailability Studies
A blind, randomized, two-way crossover bioequivalence study was performed in normal healthy male volunteers (n=24) under fasting conditions on Ramipril/Hydrochlorothiazide tablets using Pharmascience Inc. pms-RAMIPRIL-HCTZ 10 mg/25 mg tablets versus the reference product, ALTACE® HCT 10 mg/25 mg Tablets, by Sanofi Aventis Canada Inc. The pharmacokinetic data calculated for the pms-RAMIPRIL-HCTZ 10 mg/25 mg tablets and ALTACE® HCT 10 mg/25 mg tablets formulation are tabulated below:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
RAMIPRIL
Ramipril/Hydrochlorothiazide (1 x 10 mg/25 mg tablet) From measured data Uncorrected for potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval (90%) |
AUCT (ng·h/mL) | 19.002 21.594 (60.3) | 20.757 23.559 (55.8) | 91.55 | 85.78-97.69 |
AUCI (ng·h/mL) | 20.727 24.051 (62.7) | 22.918 26.340 (55.9) | 90.44 | 82.62-99.00 |
Cmax (ng/mL) | 22.002 25.395 (57.4) | 25.305 29.998 (60.6) | 86.95 | 74.43-101.57 |
Tmax§ (h) | 0.50 (0.25 – 1.00) | 0.50 (0.25 – 2.00) | ||
T½€ (h) | 1.81 (51.1) | 2.15 (47.7) | ||
*pms-RAMIPRIL-HCTZ, Pharmascience Inc., Montréal, Canada †ALTACE®HCT, Sanofi Aventis Canada Inc., Laval, Québec, Canada § Expressed as the median (range)
€ Expressed as the arithmetic mean (CV %)
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
HYDROCHLOROTHIAZIDE
Ramipril/Hydrochlorothiazide (1 x 10 mg/25 mg tablet) From measured data Uncorrected for potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval (90%) |
AUCT (ng·h/mL) | 936.45 964.83 (21.3) | 962.32 999.94 (26.5) | 97.31 | 91.46-103.54 |
AUCI (ng·h/mL) | 1034.01 1061.91 (19.9) | 1057.46 1092.35 (23.9) | 97.78 | 93.10-102.70 |
Cmax (ng/mL) | 148.05 153.79 (26.1) | 156.75 165.89 (36.9) | 94.45 | 84.40-105.69 |
Tmax§ (h) | 1.50 (1.00 – 4.00) | 1.50 (1.25 – 4.00) | ||
T½€ (h) | 10.14 (16.5) | 9.99 (15.6) | ||
*pms-RAMIPRIL-HCTZ, Pharmascience Inc., Montréal, Canada †ALTACE®HCT, Sanofi Aventis Canada Inc., Laval, Québec, Canada § Expressed as the median (range)
€ Expressed as the arithmetic mean (CV %)
Study Demographics and Trial Design
Table 4 - Summary of Patient Demographics for Clinical Trials in Specific Indication
| Study No. | Trial Design | Dosage, Route of Administration and Duration (Number of Weeks) | Study Subjects (Entered/Complete d) | Mean Age (Range) | Gender (M/F) |
HOE9829/8/ F/301/HT (Study 7) | Multicentre, double-blind, randomized, placebo run-in phase | R: 2.5 mg/od tablets; H: 12.5 mg/od tablets; R+H (fixed comb): 2.5/12.5 mg/od Oral 12 weeks | R: 218/218; H: 220/220; R+H: 222/222 | (20-75) | 329/331 |
HOE498/2/ MN/201/HT (Study 1) | Randomized, placebo-controlled, double-blind, with single-blind placebo run-in phase | P: --- R: 2.5, 5.0, or 10.0 mg/od; H: 12.5, or 25.0 mg/od; R+H: 2.5+12.5, 2.5+25.0, 5.0+25.0, 10.0+12.5, or 10.0+25.0 mg/od Oral 6 weeks | P: 44/42 R: 136/134 H: 88/85 R+H: 266/257 | 48.2 (21-68) | 302/232 |
HOE498-2 MN-302 HT (Study 5) | Multicentre, double-blind, randomized, parallel, placebo run- in phase | R: 10 mg od; H: 50 mg od; R+H: 10/50 mg od Oral 16 weeks | R: 93/75 non-responders: 35 H: 99/78 non-responders: 49 | 56 (29-80) | 99/93 |
HOE498/8/ USA/351/ HT (Study 2) | Double- blind, stratified, randomized, with 3 parallel treatment groups, placebo wash-out period | R: 5 mg/od; H: 25 mg/od; R+H: 5/25 mg/od Oral 12 weeks | R: 120/111 H: 120/114 R+H: 120/113 | (27-80) | 238/122 |
HOE498/2/M N/309/HT (Study 3) | Double-blind, multicentre. The study comprised of a 2-week placebo run-in phase | R: 5, or 10 mg/od; R+H: 5/25 mg/od Oral 10 weeks | Double-blind phase: Non-responders 5 R: 54/53 10 R: 53/50 R+H: 58/58 Responders 5 R: 59/58 | 57.0 (23-78) | 119/121 |
HOE9829/2/ D/201/HT (Study 6) | Open-label, uncontrolled, multicentre, one-year extension of HOE498/2/M N/309/HT (Study 3) | R+H (fixed comb): 5/25 or 10/50 mg/od tablet oral 52 weeks | R+H (5/25mg): 73/68; R+H (10/50mg): 3/3; R+H (5/25mg or 10/50 mg): 9/9 | (26-74) | 55/41 |
Table 4 - Summary of Patient Demographics for Clinical Trials in Specific Indication
| Study No. | Trial Design | Dosage, Route of Administration and Duration (Number of Weeks) | Study Subjects (Entered/Complete d) | Mean Age (Range) | Gender (M/F) |
HOE498/2/M N/310/HT (Study 4) | Open-label, uncontrolled, multicentre, one-year extension of HOE498/2/M N/309/HT (Study 3) | Responders: R: 5 mg/od Non-responders: R+H: 5+25 mg/od Oral 12 months | R: 38/31 R+H < 50 weeks: 38/32 R+H> 50 weeks: 83/81 | (25-78) | 86/73 |
R = Ramipril, H = Hydrochlorothiazide, od = once daily, bid = twice daily
All populations included in the 7 phase II/III safety studies were similar, male and female patients suffering from mild to moderate hypertension (WHO stage I or II hypertension).
A subgroup analysis was performed with data derived from studies 1, 2, 3, and 4 in order to assess the efficacy and/or safety of the combination of ramipril/hydrochlorothiazide in different risk groups, which included elderly, diabetic, renally insufficient, and patients with concomitant medications (non-steroidal anti-inflammatory drugs, nitrates, digitalis, and antigout agents). A total of 1,180 patients participated in studies 1 - 4.
Study Result
Table 5 - Results of All Efficacy Studies for Ramipril/Hydrochlorothiazide in Reducing Blood Pressure in Essential Hypertension
Study Treatment
Arm
# Enrolled/
Completed
Supine Mean Systolic and Diastolic BP
[Systolic/Diastolic (mm Hg)]
Primary
Endpoint Other Comments
Baseline Endpoint
(Each study varies in duration, so values are only
inserted where applicable.)
6 wks. 8 wks. 10 wks. 12 wks.
HOE982
9 –
301HT
(Study 7)
R: 2.5 mg 218/185 166.7/102.2 149.3/89.1
Supine diastolic
blood pressure –
level of response.
The data represents the per protocol analysis. The difference between R+H and H alone was not significant but were significant in the intent-to-treat analysis.
H: 12.5 mg 220/183 167.9/102.9 149.3/90.4
R+H:
2.5/12.5 mg
222/167 167.5/102.1 147.4/87.8
R= Ramipril
H= Hydrochlorothiazide
Table 5 (Continued) - Results of All Efficacy Studies for Ramipril/Hydrochlorothiazide in Reducing Blood Pressure in Essential Hypertension
Study Treatment Arm # Enrolled/
Completed
Supine Mean Systolic and Diastolic BP
[Systolic/Diastolic (mm Hg)]
Primary
Endpoint
Other Comments
Baseline Endpoint
(Each study varies in duration, so values are only
inserted where applicable.)
6 wks. 8 wks. 10 wks. 12 wks.
HOE498 –
201HT
(Study 1)
R: 2.5 mg 44/44 162.5/106.4 153.3/99.7 Change in supine
and standing
diastolic and
systolic blood
pressure.
The combinations
(5/12.5 mg, 5/25 mg and 10/12.5 mg) produced significantly greater blood pressure reductions than their respective
components at week 6 and endpoint.
R: 5 mg 48/47 161.0/106.0 149.1/100.0 R: 10 mg 44/43 157.4/107.1 146.2/98.6 H: 12.5 mg 46/45 161.3/107.2 152.6/100/.7 H: 25 mg 42/40 161.0/106.6 149.1/98.2 R+H: 2.5/12.5 mg 45/42 160.1/106.1 145.0/97.2 R+H: 2.5/25 mg 43/42 163.0/105.9 147.1/97.2 R+H: 5/12.5 mg 44/44 161.8/106.8 144.0/95.9 R+H: 5/25 mg 47/44 163.8/108.1 143.4/94.7 R+H: 10/12.5 mg 43/43 158.7/106.6 141.1/93.6 R+H: 10/25 mg 44/42 163.9/106.4 142.9/95.1 R = Ramipril
H = Hydrochlorothiazide
Table 5 (Continued) - Results of All Efficacy Studies for Ramipril/Hydrochlorothiazide in Reducing Blood Pressure in Essential Hypertension
Study Treatment
Arm
# Enrolled/
Completed
Supine mean systolic and diastolic BP
[Systolic/Diastolic (mm Hg)]
Primary
Endpoint Other Comments
Baseline Endpoint
(Each study varies in duration, so values are only
inserted where applicable.)
6 wks. 8 wks. 10 wks. 12 wks.
HOE498 –
302HT
(Study 5)
Responders: Phase 1: Change in
systolic and
diastolic supine and standing
blood pressure.
The results are for the second phase (weeks 11 – 16), except for the baseline blood pressure values. In the second phase,
responders continued with monotherapy and
nonresponders were placed on combination therapy. R: 10 mg 30 166.4/102.8 148.7/84.7 148.8/84.5 H: 50 mg 45 167.6/101.9 143.5/84.8 139.4/83.2
(N = 129) Non-responders: R+H: 10/50 mg 84 160.4/99.1 149.5/90.8
5
HOE498 –
351HT
(Study 2)
R: 5 mg 120/111 157.3/104.4 152.2/98.1 Change in
systolic and
diastolic supine and standing
blood pressure.
Subjects are stratified according to race
(blacks/nonblacks). R+H was equally effective in both blacks and non-blacks in decreasing diastolic and systolic blood pressure. H: 25 mg 120/114 159.7/104.2 145.4/93.9 R+H: 5/25 mg 120/113 158.1/104.4 141.8/91.9
R = Ramipril
H = Hydrochlorothiazide
Table 5 (Continued) - Results of All Efficacy Studies for Ramipril/Hydrochlorothiazide in Reducing Blood Pressure in Essential Hypertension
Study Treatment Arm
#
Enrolled
/
Complet
ed
Supine mean systolic and diastolic BP
[Systolic/Diastolic (mm Hg)]
Primary
Endpoint Other Comments
Baseline Endpoint
(Each study varies in duration, so values are only
inserted where applicable.)
6 wks. 8 wks. 10 wks. 12 wks.
HOE498
- 309HT
(Study 3)
Responders: Change in
systolic and
diastolic supine and standing
blood pressure.
The results are for the 2nd phase of the study. Responders continued with monotherapy and nonresponders were kept on monotherapy or placed on combination therapy.
R: 5 mg 59/58 170.7/100.9 146.6/86.5
Non-responders:
R: 5 mg 54/53 171.5/103.2 152.8/90.6 R: 10 mg 53/50 174.2/102.7 152.1/89.6 R+H: 5/25 mg 58/57 176.0/102.5 149.0/87.0
HOE9829
- 201HT
(Study 6)
R+H: 5/25 mg 73/73 Not
available,
since this is
a one-year
extension.
Change in
systolic and
diastolic supine and standing
blood pressure.
There was no evidence of an increase in mean blood pressure or of an increase in the number of nonresponders during long-term treatment. R+H: 10/50 mg 3/3 SWITCH (R+H):
5/25 or 10/50 mg
R = Ramipril
H = Hydrochlorothiazide
Table 5 (Continued) - Results of All Efficacy Studies for Ramipril/Hydrochlorothiazide in Reducing Blood Pressure in Essential Hypertension
Study Treatment
Arm
# Enrolled/
Completed
Supine mean systolic and diastolic BP
[Systolic/Diastolic (mm Hg)]
Primary
Endpoint Other Comments
Baseline Endpoint
(Each study varies in duration, so values are only
inserted where applicable.)
6 wks. 8 wks. 10 wks. 12 wks.
HOE498-
310HT
(Study 4)
R: 5 mg 38/31 Change in
systolic and
diastolic supine
and standing
blood pressure.
There was no evidence of an increase in mean blood pressure or an increase in the number of non-responders during long-term
treatment.
R+H:
5/25 mg
SWITCH (R
or R+H):
5 mg or
5/25 mg
R = Ramipril
H = Hydrochlorothiazide
DETAILED PHARMACOLOGY
Refer to pms-RAMIPRIL Product Monograph and Thiazide Diuretics Product Monograph for information.
TOXICOLOGY
Acute toxicity
Ramipril
As it has an LD50 > 10,000 mg/kg body weight in mice and rats and >1,000 mg/kg body weight in beagle hounds, oral administration of ramipril has been found to be devoid of acute toxicity.
Ramipril + Hydrochlorothiazide
The oral LD50 in rats and mice is > 10,000 mg/kg body weight, i.e., the combination ramipril + hydrochlorothiazide (1:5) is totally devoid of acute toxicity. This is consistent with the results of acute toxicity testing of the single components.
Chronic Toxicity
Ramipril
Studies involving chronic administration have been conducted in rats, dogs and monkeys. In rats, daily doses of the order of 40 mg/kg body weight lead to shifts in plasma electrolytes and to anaemia. At daily doses of ≥ 3.2 mg/kg body weight, there was some evidence of changes in renal morphology (distal tubular atrophy). However, these effects can be explained in pharmacodynamic terms and are characteristic of the substance class. Daily doses of 2 mg/kg body weight have been tolerated by rats without toxic effects. Tubular atrophy is encountered in rats, but not in dogs and monkeys.
As an expression of the pharmacodynamic activity of ramipril (a sign of increased renin production as a reaction to reduced angiotensin II formation), pronounced enlargement of the juxtaglomerular apparatus has been noted in the dog and monkey - especially at daily doses of ≥ 250 mg/kg body weight. Indications of plasma electrolyte shifts and changes in blood picture have also been found in the dog and monkey. Dogs and monkeys tolerated daily doses of 2.5 mg/kg body weight and 8 mg/kg body weight, respectively, without harmful effects.
Ramipril + Hydrochlorothiazide
With the exception of disturbances in electrolyte balance, studies conducted in rats and monkeys yielded no conspicuous findings.
Reproduction Toxicology
Ramipril
Reproduction toxicology studies in the rat, rabbit and monkey did not disclose any teratogenic properties.
Fertility was not impaired either in male or in female rats.
The administration of ramipril to female rats during the fetal period and lactation produced irreversible renal damage (dilatation of the renal pelvis) in the offspring at doses of ≥ 50 mg/kg body weight.
Ramipril + Hydrochlorothiazide:
Rats
In studies on embryotoxicity, the combination was administered to rats in daily doses of 1- 2,400 mg/kg body weight during the sensitive phase of organogenesis. Hydrochlorothiazide has been studied in a similar way alone at daily doses of 125 – 2,000 mg/kg body weight; these doses corresponded to the proportions of hydrochlorothiazide contained in the 3 highest doses of the combination.
The studies in rats showed that dams tolerated the combination administered at dose levels of ≤ 10 mg/kg body weight without complications. Doses of ≥ 150 mg/kg body weight showed toxic effects on dams and led to reduced food intake and weight development. Heart and liver weights were reduced. Clinical symptoms of toxicity and deaths occurred at dose levels of 2,400 mg/kg body weight.
At dose levels of ≥ 150 mg/kg body weight, urine excretion increased, and after 2,400 mg/kg body weight kidney weights were slightly increased. These effects are attributable to the pharmacodynamic action of hydrochlorothiazide.
A dose of 1 mg/kg body weight does not impair the development of the embryo. Doses of ≥ 10 mg/kg body weight led to a slight retardation in development of the fetus, which manifested itself in delayed skeletal ossification and, at dose levels of ≥ 150 mg/kg body weight, in reduced body weight and reduced body length. Placenta weight was also reduced.
Morphological investigations conducted in fetuses revealed increased occurrences of dilatation of the renal pelvis and the ureter as well as waved and thickened ribs at dose levels of ≥ 150 mg/kg body weight and, at levels of ≥ 600 mg/kg body weight, bent and shortened scapula and bones of the limbs.
The studies with hydrochlorothiazide alone confirm that the retardation of fetal growth is attributable to the diuretic. The other findings point to a joint effect of the 2 single components in the combination.
The study in rats revealed that the combination is somewhat more toxic than either of the single components, but without any signs of a teratogenic effect of the combination or of hydrochlorothiazide.
Other studies were conducted in rats to determine the peri- and postnatal toxicity of the combination; doses of 10 and 60 mg/kg body weight daily were given orally during the last third of pregnancy and during the 3 weeks of lactation. At doses of 10 mg/kg body weight, the drug
neither had an adverse effect on the dams' general condition, the course of pregnancy or parturition, nor did it lead to a disturbance of intrauterine and postnatal development of the progeny.
After administration of 60 mg/kg body weight, the dams reduced food intake slightly, and the pups showed slightly reduced weights at birth and during the first week thereafter. In the subsequent period, the postnatal development of the pups turned up no conspicuous findings. The incidence of dilatation of the renal pelvis (such as has been noted following higher doses of ramipril) was not increased.
Rabbits
In studies on embryotoxicity, the combination was administered to rabbits in daily doses of 0.96 - 6.00 mg/kg body weight during the sensitive phase of organogenesis.
A further group received hydrochlorothiazide (2 mg/kg; corresponding to the amount in the 2.40 mg/kg ramipril +hydrochlorothiazide dose group).
Administration of the combination in rabbits at dose levels of 0.96 mg/kg body weight led to a slight reduction in food intake and stagnation in body weight. However, it had no adverse effect on the intrauterine development in the progeny.
Following administration at dose levels of ≥ 2.40 mg/kg body weight, the dams reduced their intake of food and water and lost weight; furthermore, deaths and spontaneous abortions occurred at these dose levels and living fetuses showed slightly retarded growth at birth. No signs of external anomalies or of anomalies affecting internal organs and skeleton of the fetuses were detected which could be attributed to administration of the combination.
Hydrochlorothiazide alone administered at daily doses of 2 mg/kg body weight was tolerated by the dams and their fetuses.
From this study, it can be concluded that the combination is slightly more toxic for the damns than either component alone and that this combination did not provoke teratogenic changes.
Studies on possible impairment of fertility and reproductive capability were not conducted with the combination, since no toxic effect was to be expected on the basis of results in the single components.
Immunotoxicology
Ramipril
Toxicology studies have yielded no indication that ramipril possesses any immunotoxic effects.
Mutagenicity
Ramipril
Extensive mutagenicity testing using several test systems has yielded no indication that ramipril possesses mutagenic or genotoxic properties.
Ramipril + Hydrochlorothiazide
Mutagenicity studies were not conducted with the combination since the results of tests with each component alone have shown no evidence of any such risk.
Carcinogenicity
Ramipril
Long-term studies in rat and mouse have yielded no indication of any tumorigenic effect. Renal tubules with oxyphilic cells and tubules with oxyphilic cellular hyperplasia in rats are regarded as response to functional alterations and morphological changes, and not as a neoplastic or pre-neoplastic response.
Ramipril + Hydrochlorothiazide
Carcinogenicity studies were not conducted with the combination since the results of tests with each component alone have shown no evidence of any such risk.
REFERENCES
- 1.
Benetos A, Vasmant D, Thiéry P, et al. Effects of Ramipril on Arterial Hemodynamics. J of
Cardiovascular Pharmacology 1991, 18(Suppl 2): S153-S156.
- 2.
Burris JF. The Effect of Ramipril on Ambulatory Blood Pressure: A Multicenter Trial. J of
Cardiovascular Pharmacology 1991, 18(Suppl 2): S131-S133.
- 3.
Carré A, Vasmant D, Elmalem J, et al. Tolerability of Ramipril in a Multicenter Study of
Mild-to-Moderate Hypertension in General Practice. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S141-S143.
- 4. Heidbreder K, Froer K-L, Bauer B et al. Efficacy and Safety of Ramipril in Combination with Hydrochlorothiazide: Results of a Long-Term Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S169-S173.
- 5.
Hosie J and Meredith P. The Pharmacokinetics of Ramipril in a Group of Ten Elderly
Patients with Essential Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S125-S127.
- 6.
Lenox-Smith AJ, Street RB and Kendall FD. Comparison of Ramipril Against Atenolol in
Controlling Mild-to-Moderate Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl.2): S150-S152.
- 7. Manhem PJO, Ball SG, Morton JJ, Murray GD, Leckie BJ, Fraser R, Robertson JIS. A dose-response study of Hoe 498, a new non-sulphydryl converting enzyme inhibitor, on blood pressure, pulse rate and the renin-angiotensin-aldosterone system in normal man. Br J Clin. Pharmacol 1985, 20: 27-35.
- 8. McCarron D and The Ramipril Multicenter Study Group. 24-Hour Blood Pressure Profiles in Hypertensive Patients Administered Ramipril or Placebo Once Daily: Magnitude and Duration of Antihypertensive Effects. Clin Cardiol 1991, 14: 737-742.
- 9.
Mills TP. Ramipril: A review of the new ACE inhibitor. J of the Arkansas Medical Society,
February 1992, 88(9): 437-440.
- 10. Reinich W, Hoffmann H, Hoffmann W. Treatment of hypertension with the new ACE-inhibitor Ramipril. (Translation) Therapiewoche Österreich 1992, 7: 112-119.
- 11.
Rosenthal J, Buehler G, Koenig W, et al. Effect of Angiotensin-Converting Enzyme
Inhibition on Human Tissue Renin. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S122-S124.
- 12.
Saalbach R, Wochnik G, Mauersberger H, et al. Antihypertensive Efficacy, Tolerance, and
Safety of Ramipril in Young vs. Old Patients: A Retrospective Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S134-S136.
- 13.
Schnaper HW. Dose-Response Relationship of Ramipril in Patients with Mild-to-Moderate
Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl. 2): S128-S130.
- 14. Schreiner M, Berendes B, Verho M, et al. Antihypertensive Efficacy, Tolerance, and Safety of Long-Term Treatment with Ramipril in Patients with Mild-to-Moderate Essential Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S137-S140.
- 15.
Vasmant D, Lendresse P, Lemarie J-C, et al. Comparison of Response Rates to the
Angiotensin-Converting Enzyme Inhibitor Ramipril in Mild-to-Moderate Hypertension in a Double-Blind, Parallel-Group Study and an Open Single-Blind Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S144-S146.
- 16. Vierhapper H, Witte U, Waldhausl W. Unchanged pressor effect of norepinephrine in normal man following the oral administration of two angiotensin converting enzyme inhibitors, captopril and Hoe 498. J Hypertens 1986, 4: 9-11.
- 17.
Product monograph for PrALTACE® HCT (Valeant Canada LP) Date of revision: April 12,
2018, Control No.: 212642.