


Product Monograph - Rebif (Emd Serono, A Division of Emd Inc., Canada, 11 mcg / 2 mL)
INDICATIONS AND CLINICAL USE
Multiple Sclerosis: Rebif® is indicated for the treatment of relapsing forms of multiple sclerosis, to reduce the number and severity of clinical exacerbations, slow the progression of physical disability, reduce the requirement for steroids, and reduce the number of hospitalizations for treatment of multiple sclerosis and reduction in T1-Gd enhanced and T2 (burden of disease) as seen on MRI.
Relapsing forms of multiple sclerosis include the subgroups of MS in which patients still experience recurrent attacks of neurological dysfunction including traditional RRMS but also SPMS patients still experiencing relapses.
| Although | Rebif® | d | id not affect progression of disability in SPMS, the clinical trial has shown that | ||||||||||||||||
| secondary | progressive | MS | patients | who | st | ill experience relapses, had a statistically significant | |||||||||||||
| improvement | on | relap | se rate and on MRI measures of disease activity as compared to patients on | ||||||||||||||||
| placebo. | |||||||||||||||||||
Rebif® has not yet been investigated in patients with primary progressive multiple sclerosis and should not be administered to such patients.
Condyloma acuminatum: Rebif® is best suited for the patient who has less than nine lesions, and who has failed several prior treatments. In the case of patients with nine or more lesions, if the first Rebif® treatment is successful, the remaining lesions could be treated with a second course of Rebif® therapy. Rebif® should also be considered for the treatment of condyloma acuminatum in patients for whom the side-effects from other treatments, e.g., scarring, are of concern. While not all patients who were treated with Rebif® attained a complete response, patients whose lesions decreased in size and had at least a partial response may have also benefitted from treatment because lesion shrinkage may facilitate subsequent management with other therapies, as has been reported with IFN-alpha.
CONTRAINDICATIONS
Rebif® (Interferon beta-1a) is contraindicated in patients with a known hypersensitivity to natural or recombinant interferon beta, albumin (human), or any other component of the formulation.
Rebif® is contraindicated in pregnant patients (see WARNINGS).
WARNINGS
Rebif® (Interferon beta-1a) should be used under the supervision of a physician. The first injection should be performed under the supervision of an appropriately qualified health care professional. Relapsing forms of Multiple Sclerosis
Depression
Depression and suicidal ideation are known to occur in increased frequency in the multiple sclerosis population and in association with interferon use, including Rebif®. Some association of increased depression has been noted with interferon use. However, clinical trial data with Rebif has not shown an increase in depression compared to placebo-treated patients. Patients treated with Rebif® should be advised to immediately report any symptoms of depression and/or suicidal ideation to their prescribing physician. Patients exhibiting depression should be monitored closely during therapy with Rebif® and treated appropriately. Cessation of therapy with Interferon beta-1a should be considered (see CONTRAINDICATIONS).
Hepatic Injury
Isolated, life-threatening cases of acute hepatic failure have been reported with Rebif therapy. Symptomatic hepatic dysfunction, primarily presenting as jaundice, has been reported as a rare complication of Rebif® use. Several possible mechanisms may explain the effect of Rebif® on the liver (including direct toxicity, indirect toxicity via release of cytokines and/or autoimmunity. Asymptomatic elevations of transaminases (particularly ALT) is common with interferon therapy (see ADVERSE REACTIONS). Dose reduction or discontinuation should be considered if ALT rises 5 times above the ULN.
Anaphylaxis
Anaphylaxis has been reported as a rare complication of Rebif® use. Other allergic reactions have included skin rash, angioedema, and urticaria, and have ranged from mild to severe without a clear relationship to dose or duration of exposure. Several allergic reactions, some severe, have occurred after prolonged use.
Pregnancy and Lactation
Rebif® should not be administered in case of pregnancy and lactation. There are no adequate and well-controlled studies of Rebif® in pregnant women. In the clinical trials there were 2 spontaneous abortions observed and 5 fetuses carried to term among 7 women in the Rebif® groups. There have been cases of spontaneous abortion in the post-marketing setting. In cynomolgous monkeys administered doses approximately 2 times the cumulative weekly human dose (based on either body weight or surface area), Rebif® treatment has been associated with significant increases in embryolethal or abortifacient effects either during the period of organogenesis (gestation day 21-
- 89) or later in pregnancy. There were no fetal malformations or other evidence of teratogenesis noted in these studies; however, it is not known if teratogenic effects exist in humans. These effects are consistent with the abortifacient effects of other type I interferons. Patients should be advised about the abortifacient potential of Rebif®.
Fertile women receiving Rebif® should be advised to take adequate contraceptive measures. It is not known if interferon alter the efficacy of oral contraceptives. Patients planning for pregnancy and those becoming pregnant should be informed of the potential hazards of interferons to the foetus and Rebif® should be discontinued (see CONTRAINDICATIONS and also PRECAUTIONS: Information to be provided to the patient).
Nursing Women: It is not known whether Rebif® is excreted in human milk. Because of the potential for serious adverse reactions in nursing infants, a decision should be made either to discontinue nursing or to discontinue Rebif® therapy.
Cardiac Disease
Patients with cardiac disease, such as angina, congestive heart failure or arrhythmia, should be closely monitored for worsening of their clinical condition during initiation and continued therapy with Rebif®. Symptoms of the flu-like syndrome associated with Rebif® may prove stressful to patients with cardiac conditions.
Condyloma
All injections should be administered by a qualified health care professional.
PRECAUTIONS General
Patients should be informed of the most common adverse reactions associated with interferon beta administration, including symptoms of the flu-like syndrome (see ADVERSE REACTIONS). These symptoms tend to be most prominent at the initiation of therapy and decrease in frequency and severity with continued treatment.
Caution should be exercised when administering Rebif® (interferon-beta-1a) to patients with pre-existing seizures disorder (see CONTRAINDICATIONS). For patients without a pre-existing seizure disorder who develop seizures during therapy, an etiologic basis should be established and appropriate anti-convulsant therapy instituted prior to continuing treatment with Rebif®. The effect of Rebif® administration on the medical management of patients with seizure disorder is unknown.
Serum neutralising antibodies against Rebif® (interferon beta-1a) may develop. The precise incidence and clinical significance of antibodies is as yet uncertain (see ADVERSE REACTIONS).
Intralesional injections can be painful to some patients treated for condyloma acuminata. In such cases an anaesthetic cream such as lidocaine-prilocaine can be used.
Pediatric use
There is no controlled clinical experience with Rebif® in children under 16 years of age with multiple sclerosis and therefore Rebif® should not be used in this population.
Patients with Special Diseases and Conditions
Caution should be used and close monitoring considered when administering Rebif® to patients with severe renal failure, patients with severe myelosuppression, and patients with cardiac disease (see WARNINGS).
Drug Interaction
No formal drug interaction studies have been conducted with Rebif® in humans. Interferons have been reported to reduce the activity of hepatic cytochrome p450-dependent enzymes in humans and animals. Caution should be exercised when administering Rebif® in combination with medicinal products that have a narrow therapeutic index and are largely dependent on the hepatic cytochrome p450 system for clearance, e.g. antiepileptics and some classes of antidepressants. The interaction of Rebif® with corticosteroids or ACTH has not been studied systematically. Clinical studies indicate that multiple sclerosis patients can receive Rebif® and corticosteroids or ACTH during relapses. Rebif® should not be mixed with other drugs in the same syringe.
Relapsing forms of multiple sclerosis: Laboratory abnormalities are associated with the use of interferons. Therefore, in addition to those laboratory tests normally required for monitoring patients with multiple sclerosis, liver enzymes should be monitored at baseline, every month for the first 6 months and every 6 months thereafter (see WARNINGS). Complete and differential white blood cell counts, platelet counts and blood chemistries are also recommended during Rebif® therapy. These tests should be performed at baseline, months 1, 3 and 6, and every 6 months thereafter. Patients being treated with interferon beta may occasionally develop new or worsening thyroid abnormalities. Thyroid testing should be performed at baseline and every 6 months. In case of abnormal results or in patients with a past history of thyroid dysfunction, any necessary treatment and more frequent testing should be performed as clinically indicated (see ADVERSE REACTIONS).
Condyloma acuminata: Same as relapsing forms of multiple sclerosis but tend not to be as severe because of dose and length of treatment.
Information to be provided to the patient
Patient should be informed of the potential risk of liver injury with Rebif therapy, be made acquainted with the signs and symptoms of such injury and be informed of the requirement for frequent laboratory testing.
Patients should be informed of the symptoms suggesting liver dysfunction, such as loss of appetite accompanied by other symptoms such as malaise, fatigue, nausea, vomiting, abdominal pain, dark urine, jaundice or pruritus. They should be advised to consult with a physician immediately if such symptoms arise.
Flu-like symptoms (fever, headache, chills, muscle aches) are not uncommon following initiation of therapy with Rebif. Acetaminophen or ibuprofen may be used for relief of flu-like symptoms. Patients should contact their physician or pharmacist if they experience any undesirable effects.
Depression may occur in patients with multiple sclerosis and may occur while patients are taking Rebif®. Some association of increased depression has been noted with interferon use. However, clinical trial data with Rebif has not shown an increase in depression compared to placebo-treated patients. Patients should be asked to contact their physician should they feel depressed. Patients should be advised not to stop or modify their treatment unless instructed by their physician.
Female patients should be advised about the abortifacient potential of Rebif® and instructed to take adequate contraceptive measures (see CONTRAINDICATIONS and see WARNINGS).
Instruction on self-injection technique and procedures: patients treated for relapsing forms of multile sclerosis should be instructed in the use of aseptic technique when administering Rebif®. Appropriate instruction for reconstitution lyophilised formulation of Rebif® and self-injection should be given including careful review of the Rebif® patient leaflet. The first injection should be performed under the supervision of an appropriately qualified health care professional. Patients should be advised of the importance of rotating sites of injection with each dose, to minimize the likelihood of severe injection site reactions or necrosis and not to inject into an area that appears abnormal. Patients should be advised to consult with their physician should they develop multiple lesions and/or experience any break in the skin, which may be associated with swelling or drainage of fluid from the injection site, as a decision may be required to discontinue Rebif® until healing has occurred. Patients with single lesions may be advised to continue provided that necrosis is not too extensive. Patients should be cautioned against the re-use of needles or syringes and instructed in safe disposal procedures. A puncture resistant container for disposal of used needles and syringes should be supplied to the patient along with instructions for safe disposal of full containers.
In the controlled MS trial injection site reactions were commonly reported by patients at one or more times during therapy (see ADVERSE REACTIONS). In general, they did not require discontinuation of therapy, but the nature and severity of all reported reactions should be carefully assessed. Patient understanding and use of aseptic self-injection technique and procedures should be periodically re-evaluated.
Certain laboratory tests may change: the number of white blood cells or platelets may decrease and liver function tests may be disturbed. Patients should be informed of the potential risk of liver injury with Rebif® therapy, and of the requirement for frequent laboratory testing (see WARNINGS). Patients should be informed of the symptoms suggesting liver dysfunction, such as loss of appetite accompanied by other symptoms such as nausea, vomiting, and jaundice, and advised to consult with their physician immediately should such symptoms arise.
ADVERSE REACTIONS
Multiple Sclerosis
As with other interferon preparations, flu-like symptoms are not uncommon. The use of interferon beta may cause flu-like syndrome, asthenia, pyrexia, chills, arthralgia, myalgia, headache, and injection site reactions.
Less frequent adverse reactions include cold sores, stuffy nose, light headedness, mucosal irritation, haematological disorders (leukopenia, lymphopenia, granulocytopenia), and alterations in liver function tests such as elevated AST and ALT. These effects are usually mild and reversible. Fever and flu-like symptoms can be treated with acetaminophen or ibuprofen. Depending on the severity and persistence of the side-effects, the dose may be lowered or temporarily interrupted, at the discretion of the physician.
Most injection site reactions are mild to moderate. Allergic reactions, such as pruritus, rash, erythematous rash and maculo-papular rash may occur. Cases of skin ulceration/necrosis at the site of injection have been reported with long term treatment (see PRECAUTIONS: Information to be provided to the patient).
Anaphylaxis has also been observed with the use of Rebif® (see WARNINGS).
Serious adverse hepatic reactions such as hepatitis, with or without jaundice, have been rarely reported and isolated cases of acute hepatic failure have been reported (see CONTRAINDICATIONS and see WARNINGS).
Occasional thyroid dysfunction, generally transient and mild, may occur during the first year of treatment, particularly in patients with pre-existing thyroiditis (see PRECAUTIONS: Laboratory Tests).
The adverse events experienced during the first two years of the PRISMS study are listed below, by WHOART System Organ Class. The most common amongst the injection site reactions was in the form of mild erythema. The majority of the other injection site reactions were also mild in the 2 Rebif® groups. Necrosis was reported in 8 patients treated with Rebif®. Two of these patients were in the 66µg weekly and six in the 132µg weekly groups. All patients completed the planned treatment period, with only 1 requiring temporary dose reductions and another patient stopping treatment for 2 weeks. Those that required treatment, received antibiotics. Adverse events experienced by patients enrolled in the PRISMS study.
| Body System | Preferred term | Placebo | Rebif® 66µg weekly | Rebif® 132µg weekly |
| Application site disorders | Injection site inflammation (a)(b) Injection site reaction (a)(b) Injection site pain (b) | 15.0% 13.4% 14.4% | 65.6% 31.2% 20.1% | 65.8% 34.8% 22.8% |
| Body as a whole – General disorders | Influenza-like symptoms Fatigue Fever (a)(b) Leg pain Rigors (b)(c) | 51.3% 35.8% 15.5% 14.4% 5.3% | 56.1% 32.8% 24.9% 10.1% 6.3% | 58.7% 41.3% 27.7% 13.0% 13.0% |
| Centr & periph nervous system disorders | Headache Dizziness Paraesthesia Hypoaesthesia | 62.6% 17.6% 18.7% 12.8% | 64.6% 14.3% 19.6% 12.2% | 70.1% 16.3% 16.3% 7.6% |
| Respiratory system disorders | Rhinitis Upper Resp Tract Infection Pharyngitis (b) Coughing Bronchitis | 59.9% 32.6% 38.5% 21.4% 9.6% | 52.4% 36.0% 34.9% 14.8% 10.6% | 50.5% 29.3% 28.3% 19.0% 9.2% |
| Gastro-intestinal system disorders | Nausea Abdominal pain Diarrhoea Vomiting | 23.0% 17.1% 18.7% 12.3% | 24.9% 22.2% 17.5% 12.7% | 24.5% 19.6% 19.0% 12.0% |
| Musculo-skeletal system disorders | Back pain Myalgia Arthralgia Skeletal pain | 19.8% 19.8% 17.1% 10.2% | 23.3% 24.9% 15.3% 14.8% | 24.5% 25.0% 19.0% 9.8% |
| Psychiatric disorders | Depression Insomnia | 27.8% 21.4% | 20.6% 19.6% | 23.9% 23.4% |
| White cell and res disorders | Lymphopenia (a)(b) Leucopenia (a)(b)(c) Granulocytopenia (a)(b) Lymphadenopathy | 11.2% 3.7% 3.7% 8.0% | 20.1% 12.7% 11.6% 11.1% | 28.8% 22.3% 15.2% 12.0% |
| Skin and appendages disorders | Pruritus | 11.8% | 9.0% | 12.5% |
| Liver and biliary system disorders | ALT increased (a)(b) AST increased (a)(b)(c) | 4.3% 3.7% | 19.6% 10.1% | 27.2% 17.4% |
| Urinary system disorders | Urinary tract infection | 18.7% | 18.0% | 16.8% |
| Vision disorders | Vision abnormal | 7.0% | 7.4% | 13.0% |
| Secondary terms | Fall | 16.0% | 16.9% | 15.8% |
(a) Significant difference between placebo and Rebif® 66µg weekly groups (p≤0.05)
(b) Significant difference between placebo and Rebif® 132µg weekly groups (p≤0.05)
(c) Significant difference between Rebif® 66µg and Rebif® 132µg weekly groups (p≤0.05)
In addition to the above listed adverse events, the following events have been experienced less frequently, in one or both of the relapsing-remitting multiple sclerosis studies: asthenia, fluid retention, anorexia, gastroenteritis, heartburn, paradentium affections, dental abcess or extraction, stomatitis, glossitis, sleepiness, anxiety, irritability, confusion, lymphadenopathy, weight gain, bone fracture, dyspnoea, cold sores, fissure at the angle of the mouth, menstrual disorders, cystitis, vaginitis.
After 2 years, the placebo patients were switched to Rebif®, and along with the patients for the Rebif® treatment groups, they were treated for an additional two years. Listed below by WHOART System Organ Class, are the proportion of patients reporting the most common adverse events during years 3 and 4 of treatment. The results are similar to those obtained in the original phase of the study. The findings indicate that the incidence of interferon-related adverse events diminishes somewhat with continued exposure to the medication.
Cases of necrosis were rare and not a cause of drop-out. For Rebif® 66µg weekly, there was one episode of skin necrosis per 92 years of exposure or per 14,100 injections. The comparable figures for Rebif® 132 µg weekly are 1 episode of necrosis per 61 years of exposure or per 9,300 injections.
| Body System | Preferred term | Placebo/66 (n=85) | Placebo/132 (n=87) | Rebif® 66µg weekly (n=167) | Rebif® 132µg weekly (n=167) |
| Application site disorders | Injection site inflammation Injection site reaction Injection site pain | 65.9% 28.2 18.8 | 65.5 37.9 21.8 | 56.9 29.9 15.0 | 66.5 31.7 13.8 |
| Body as a whole - General disorders | Influenza-like symptoms Fatigue Fever Leg pain Trauma Hypertonia Pain | 42.4 34.1 14.1 8.2 15.3 14.1 4.7 | 60.9 36.8 14.9 12.6 5.7 11.5 14.9 | 50.3 24.6 15.6 6.6 14.4 10.8 4.2 | 42.5 27.5 12.0 7.8 11.4 9.6 4.2 |
| Centr & periph nervous system Disorders | Headache Dizziness Paraesthesia Hypoaesthesia | 44.7 4.7 15.3 7.1 | 55.2 11.5 13.8 13.8 | 46.7 13.2 10.2 7.2 | 46.7 12.6 7.8 9.0 |
| Respiratory system disorders | Rhinitis Upper Resp Tract Infection Pharyngitis Coughing Sinusitis | 38.8 18.8 23.5 5.9 8.2 | 29.9 14.9 12.6 11.5 11.5 | 39.5 22.8 19.8 8.4 5.4 | 33.5 20.4 15.0 13.8 10.2 |
| Gastro-intestinal system disorders | Nausea Abdominal pain Diarrhoea Constipation | 12.9 8.2 5.9 14.1 | 19.5 16.1 8.0 9.2 | 10.8 13.2 12.0 6.0 | 11.4 10.8 9.0 7.2 |
| Musculo-skeletal system disorders | Back pain Myalgia Arthralgia Muscle weakness Skeletal pain | 14.1 21.2 16.5 12.9 8.2 | 20.7 23.0 18.4 17.2 11.5 | 20.4 15.6 12.6 7.2 7.2 | 22.2 14.4 18.0 9.6 6.6 |
| Psychiatric disorders | Depression Insomnia | 29.4 22.4 | 27.6 21.8 | 23.4 16.2 | 25.1 21.6 |
| White cell and res disorders | Lymphopenia Leucopenia Granulocytopenia Lymphadenopathy | 22.4 16.5 9.4 2.4 | 23.0 14.9 10.3 14.9 | 19.8 12.0 7.8 8.4 | 25.7 13.8 12.0 10.2 |
| Liver and biliary system disorders | ALT increased | 11.8 | 14.9 | 13.8 | 12.6 |
| Urinary system disorders | Urinary tract infection | 8.2 | 14.9 | 16.2 | 13.8 |
Asymptomatic laboratory abnormalities were reported frequently with interferon dosing over the 4 years. Of the abnormalities noted, the cytopenias and abnormalities ofliver function showed dose-related differences. Lymphopenia occurred in 35% of high dose patients and 27% of low dose patients. Thrombocytopenia was seen in 2.6% of patients on low dose, and 8.2% of patients on high dose. Differences in the frequency of abnormal liver enzymes were seen which included elevated ALT (24% for low dose vs. 30% for high dose, p=0.07) and elevated AST (11% vs. 20%, p=0.03). Severe elevations are uncommon and not different between dose groups. These data suggest that there is only minimal evidence of significant dose-dependent lab abnormalities with interferon therapy in MS patients.
After 4 years of therapy, 23.7% of the low dose and 14.3% of the high-dose patients had developed persistent neutralising antibodies (p = 0.024, 44µg vs. 22 µg), the vast majorityof which (91%) develop within 24 months. The lower incidence in the high dose group may be due to the phenomenon of high-zone tolerance. While continuing interferon treatment, 20.0% of low-dose Nab+ patients reverted, while 25.7% of high-dose Nab+ patients reverted. The neutralising antibodies were associated with reduced clinical efficacy during years 3 and 4 and reduced MRI efficacy over 4 years.
The table below presents adverse events that were reported in at least 10% of the patients in any treatment group of the SPECTRIMS study; the AEs are listed by WHOART system organ class and preferred term (sorted by preferred term in order of frequency). The most frequently reported adverse event was injection site inflammation, which occurred in 67% of both treated groups compared to 16% for placebo. Lower frequencies of the closely associated but more symptomatic injection site reactions were reported in 3 to 4 times as many treated patients as placebo patients. Injection site necrosis was seen in 3.3% and 8.8% of patients in the 22 mg and 44 mg groups respectively, but almost always as a single event per patient. The rate of necrosis was 1/3800 injections for high-dose and 1/9600 for low-dose therapy. Liver function abnormalities were also reported 3 to 4 times more commonly with active therapy. The haematopoietic system was also affected, with increased reports of leucopenia, granulocytopenia and lymphopenia associated with active therapy and most prominently with the higher dose. These haematopoietic abnormalities are expected side-effects of interferon therapy. Increased reports of anaemia and thrombocytopenia were noted with treatment, but these events occurred in less than 10% of patients. Adverse events experienced by patients enrolled in the SPECTRIMS study.
| Body System | Preferred term | Placebo | Rebif® 66µg weekly | Rebif® 132µg weekly |
| Application site disorders | Injection site inflammation (a)(b) Injection site reaction (a)(b)(c) Injection site pain Injection site bruising (a) | 15.6% 7.8% 18.0% 16.1% | 66.5% 21.1% 17.2% 8.1% | 67.2% 31.9% 22.5% 9.8% |
| Body as a whole – General disorders | Influenza-like symptoms Headache ( c ) Fatigue (b) (c) Fever (c) Leg pain Asthenia (c) | 52.2% 56.6 32.2% 11.7% 9.3% 9.8% | 50.7% 52.2 33.0% 14.4% 11.5% 5.7% | 49.5% 63.2 43.1% 19.1% 12.3% 12.3% |
| Centr & periph nervous system disorders | Hypertonia Dizziness Paraesthesia Hypoaesthesia | 26.8% 18.0% 13.2% 9.3% | 24.4% 16.3% 8.1% 10.0% | 30.4% 17.2% 9.3% 8.3% |
| Respiratory system disorders | Rhinitis Upper Resp Tract Infection Pharyngitis | 41.5% 33.2% 20.0% | 38.3% 31.1% 19.6% | 33.3% 26.0% 17.2% |
| Gastro-intestinal system disorders | Nausea (b) Abdominal pain Diarrhoea Constipation | 26.3% 18.0% 15.6% 19.0% | 23.9% 14.8% 18.7% 14.8% | 17.6% 15.2% 13.7% 13.2% |
| Musculo-skeletal system disorders | Myalgia Arthralgia Back pain Muscle weakness | 23.9% 25.4% 22.4% 18.0% | 24.9% 24.4% 21.5% 17.2% | 27.9% 23.0% 22.1% 16.7% |
| Psychiatric disorders | Depression Insomnia | 28.8% 22.0% | 32.1% 20.6% | 34.8% 23.5% |
| White cell and res disorders | Lymphopenia (b) Leucopenia (a)(b)(c) Granulocytopenia (a)(b) | 15.1% 4.9% 2.0% | 21.5% 11.0% 9.1% | 26.0% 21.1% 13.2% |
| Liver and biliary system disorders | ALT increased (a)(b) ASTincreased (a)(b) | 7.3% 3.4% | 21.1% 11.5% | 23.0% 13.2% |
| Urinary system disorders | Urinary tract infection Cystitis | 26.3% 12.7% | 34.4% 17.2% | 27.0% 10.8% |
| Vision disorders | Vision abnormal (b) (c) | 11.7% | 10.5% | 4.9% |
| Secondary terms | Traumas Nos | 28.3% | 24.9% | 23.0% |
(a) Significant difference between placebo and Rebif® 66µg weekly groups (p=0.05)
(b) Significant difference between placebo and Rebif® 132µg weekly groups (p=0.05)
(c) Significant difference between Rebif® 66µg and Rebif® 132µg weekly groups (p=0.05)
The data indicate that Rebif® is safe when administered chronically even at high dose. Furthermore, studies with Rebif® have included patients with disability ranging from none to severe, age ranging from 18 to 55 at study start and in the forms of MS (SPMS, RRMS) that comprise over 80% of all MS patients.
In the ETOMS study adverse events were reported more frequently in patients assigned Rebif® than in those assigned placebo. These events included injection-site inflammation (60% vs 12%), fever (28% vs 12%), myalgia (17% vs 9%) and chills (11% vs 5%). Serious adverse events were reported in five patients in the placebo group and six in the interferon beta-1a group.
Condyloma acuminata
Most common adverse events for patients treated for Condyloma Acuminata
| Body System/Preferred term | Preferred Term | Trial 1 | Trial 2 | Trial 3 | Trial 4 |
| n=25 | n=52 | n=50 | n=65 | ||
| Body as a whole - general | asthenia | 24.0% | 3.8% | 36.0% | 15.4% |
| fever | 8.0% | 21.2% | 4.0% | 0.0% | |
| flu-syndrome | 4.0% | 7.7% | 24.0% | 26.1% | |
| injection site reaction | 8.0% | 11.5% | -- | -- | |
| injection site inflammation | -- | 5.8% | -- | -- | |
| headache | 28.0% | 42.3% | 20.0% | 36.9% | |
| bodily discomfort | -- | 15.4% | -- | -- | |
| back pain | -- | 9.6% | -- | 10.8% | |
| pain | -- | -- | -- | 9.2% | |
| pelvic pain | 4.0% | -- | 6.0% | -- | |
| chills | -- | 28.8% | -- | 6.2% | |
| malaise | -- | 1.9% | 16.0% | 1.5% | |
| injection site pain | 4.0% | 36.5% | 66.0% | 13.8% | |
| non-inflammatory swelling | -- | 7.7% | -- | -- | |
| fatigue | -- | 28.8% | -- | -- | |
| Digestive system | nausea | 8.0% | 17.3% | -- | 1.5% |
| vomiting | 8.0% | 1.9% | -- | 3.0% | |
| Musculoskeletal system | myalgia | 12.0% | 3.8% | 2.0% | 9.2% |
| muscle ache | -- | 26.9% | -- | -- | |
| muscle pain | -- | 1.9% | -- | -- | |
| Respiratory system | pharyngitis | 16.0% | 0.0% | -- | 3.0% |
Other adverse events were experienced by less than 5% of the patients, and included eye pain, skin disorder, rhinitis, bronchitis, coughing, diarrhoea, abdominal pain, postural hypotension, palpitation, vasodilatation, rectal disorder, lymphocytosis, thrombocytopenia, delirium, somnolence, joint pain, joint stiffness, lightheadedness, paraesthesia distal, disorientation, irritability, sleeplessness, lethargy, bruise, purpura, sweating increased, shortness of breath, upper respiratory tract infection, tachycardia, flushing, urethral pain, infection, chest pain, lymphadenopathy, PBI increased, arthralgia, dizziness, nervousness, tremor, abnormal vision, vulvovaginal disease, balanitis, penis disease, testis disease, urethritis, infection urinary tract, vaginitis, leukopenia, herpes simplex, pruritis, rash mac pap, skin neoplasia, rash.
Post-marketing Surveillance
The vast majority of the adverse reactions of Rebif in multiple sclerosis have been identified from the clinical trials and are summarized in the above “placebo-controlled study tables”. The adverse reactions reported with marketed use of Rebif that are not already mentioned in the clinical study tables are hepatitis systemic allergic reactions (angioedema, urticaria), and skin reactions such as erythema multiforme and erythema-multiforme-like. These events are most likely uncommon to very rare. Injection site abscess and injection site induration have also been reported. These reactions have been identified with post-marketing surveillance in an estimated patient population corresponding to 105,000 patient-years.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
No case of overdose has thus far been described. However, in case of overdosage, patients should be hospitalised for observation and appropriate supportive treatment should be given.
DOSAGE AND ADMINISTRATION
RELAPSING FORMS OF MULTIPLE SCLEROSIS:
Before initiating a patient on Rebif® therapy, please review completely the CONTRAINDICATIONS section of this Product Monograph.
The recommended dose is 44 µg given 3 times per week by subcutaneous injection. The dose can be reduced to 22 µg tiw if the patient is not able to tolerate the higher dose.
Treatment should be initiated under supervision of a physician experienced in the treatment of the disease. When first starting treatment with Rebif®, in order to allow tachyphylaxis to develop thus reducing adverse events, it is recommended that 20% of the total dose be administered during the initial 2 weeks of therapy, 50% of total dose be administered in week 3 and 4, and the full dose from the fifth week onwards.
Please also review the WARNINGS and PRECAUTIONS sections and ensure appropriate monitoring of patients with depression, hepatic dysfunction, a history of seizures, cardiac disease, renal dysfunction, thyroid dysfunction, myelosuppression, and female patients of child-bearing potential.
| Patients should be advised of Rebif’s side-effects and instructed on the use of aseptic technique | |||||||||||
| when | administering | Rebif®. | The Rebif® Patient Leaflet should be carefully reviewed with all | ||||||||
| patients, | and | patients | should be educated on self-care and advised to keep the Leaflet for | ||||||||
| continued reference during Rebif® therapy. | |||||||||||
At the present time, it is not known for how long patients should be treated. Safety and efficacy with Rebif® have been demonstrated following 4 years of treatment. Therefore, it is recommended that patients should be evaluated after 4 years of treatment with Rebif® and a decision for longer-term treatment be made on an individual basis by the treating physician.
Preparation of Solution: Lyophilized formulation (Relapsing forms of-Multiple Sclerosis)
Reconstitute the contents of a vial of Rebif® with 0.5 mL of the accompanying sterile diluent (see table below for diluent volume and resulting concentration). The reconstituted solution should be used immediately.
Reconstitution Table
Strength Volume of Diluent Approximate Nominal to be added to vial available volume concentration/mL
11 :g 0.5 mL 0.5 mL 22 :g 44 :g 0.5 mL 0.5 mL 88 :g
Preparation of Solution: Liquid formulation
The liquid formulation in a pre-filled syringe is ready for use. These syringes are graduated to facilitate therapy initiation. The pre-filled syringes contain 8.8 µg, 22µg and 44µg of Rebif® respectively. The pre-filled syringes are ready for subcutaneous use only.
CONDYLOMA ACUMINATUM: The recommended posology is 3.67:g per lesion three times per week for 3 weeks. The recommended route of administration is intra- or peri-lesional. The pre-filled syringes are not to be used for this indication.
Preparation of Solution: Lyophilized formulation (Condyloma acuminatum)
Reconstitute the contents of a vial of Rebif® in sterile diluent in order to obtain a final concentration of 3.7µg per 0.1 mL solution. The reconstituted solution should be used immediately.
Reconstitution Table
Strength Volume of Diluent Approximate Nominal to be added to vial available volume concentration/mL
11 :g 0.3 mL 0.3 mL 37 :g 44 :g 1.2 mL 1.2 mL 37 :g
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE
Proper or Common Name: BAN: Interferon beta-1a
INN: Interferon beta-1a
USAN: Interferon beta-1a
Chemical Name: Not applicable
Structural Formula: The full amino acid sequence is as follows : 1
11
21
31
41
51
61
71
81
91
101
111
121
131
141
151
161
Met-Ser-Tyr-Asn-Leu-Leu-Gly-Phe-Leu-Gln
Arg-Ser-Ser-Asn-Phe-Gln-Cys-Gln-Lys-Leu
Leu-Trp-Gln-Leu-Asn-Gly-Arg-Leu-Glu-Tyr
Cys-Leu-Lys-Asp-Arg-Met-Asn-Phe-Asp-Ile
Pro-Glu-Glu-Ile-Lys-Gln-Leu-Gln-Gln-Phe
Gln-Lys-Glu-Asp-Ala-Ala-Leu-Thr-Ile-Tyr
Glu-Met-Leu-Gln-Asn-Ile-Phe-Ala-Ile-Phe
Arg-Gln-Asp-Ser-Ser-Ser-Thr-Gly-Trp-Asn*
Glu-Thr-Ile-Val-Glu-Asn-Leu-Leu-Ala-Asn
Val-Tyr-His-Gln-Ile-Asn-His-Leu-Lys-Thr
Val-Leu-Glu-Glu-Lys-Leu-Glu-Lys-Glu-Asp
Phe-Thr-Arg-Gly-Lys-Leu-Met-Ser-Ser-Leu
His-Leu-Lys-Arg-Tyr-Tyr-Gly-Arg-Ile-Leu
His-Tyr-Leu-Lys-Ala-Lys-Glu-Tyr-Ser-His
Cys-Ala-Trp-Thr-Ile-Val-Arg-Val-Glu-Ile
Leu-Arg-Asn-Phe-Tyr-Phe-Ile-Asn-Arg-Leu
Thr-Gly-Tyr-Leu-Arg-Asn
* Asn-80 N-glycosylation site
Molecular Weight: Approximately 22,500 daltons, identical to the natural human IFN-beta
Physical Form: IFN-beta-1a is a glycoprotein of 166 amino acids, it has 3 cysteines at positions
17, 31 and 141, a single disulphide bridge and an N-linked carbohydrate moiety primarily of the biantennary complex type attached to Asn-80.
Bulk hIFN-beta-1a is a clear, colourless to yellowish solution.
pH: 3.8 +/- 0.5
COMPOSITION
Lyophilized formulation
Each 3 mL vial of sterile lyophilized powder contains Interferon beta-1a, albumin (human), mannitol and sodium acetate, as indicated in the table below. Acetic acid and sodium hydroxide are used to adjust the pH.
| Interferon beta-1a | Albumin (Human) | Mannitol | Sodium acetate |
| 11 :g | 9 mg | 5 mg | 0.2 mg |
| 44 :g | 9 mg | 5 mg | 0.2 mg |
Rebif® (Interferon beta-1a) is supplied with a 2 mL diluent ampoule containing 2 mL of 0.9% in NaCl in Water for Injection. No preservatives are present.
Liquid formulation
The liquid formulation is supplied in syringes containing 0.2 mL or 0.5 mL of solution. Each syringe contains Interferon beta-1a, albumin (human), mannitol and 0.01 M sodium acetate buffer, as indicated in the table below. The solution does not contain preservatives.
| Interferon beta-1a | Albumin (Human) | Mannitol | 0.01M Sodium acetate buffer |
| 8.8 :g | 0.8 mg | 10.9 mg | q.s. to 0.2 mL |
| 22 :g | 2 mg | 27.3 mg | q.s. to 0.5 mL |
| 44 :g | 4 mg | 27.3 mg | q.s. to 0.5 mL |
STABILITY AND STORAGE RECOMMENDATIONS
Lyophilized formulation: Refer to the date indicated on the labels for the expiry date. Rebif® (Interferon beta-1a) lyophilized product should be stored at 2-8°C.
Liquid formulation: Refer to the date indicated on the labels for the expiry date. Rebif® liquid in a pre-filled syringe should be stored at 2-8°C. Rebif® syringes may be stored for a limited period at room temperature (up to 25ºC), but not more than 1 month. Do not freeze.
RECONSTITUTED SOLUTIONS
Lyophilized formulation: Lyophilized Rebif® should be reconstituted with 0.9 % NaCl in Water for Injection (supplied in 2 mL neutral glass ampoules containing 2.0 mL). The reconstituted solution should be administered immediately. Although not recommended, it may be used later during the day of reconstitution if stored in a refrigerator (2-8°C). Do not freeze. The reconstituted solution may have a yellow colouration which is a normal product characteristic.
Liquid formulation: The liquid in the pre-filled syringe is ready for use.
PARENTERAL PRODUCTS
See "Preparation of Solution" for table of reconstitution.
AVAILABILITY OF DOSAGE FORM
Rebif® (Interferon beta-1a) is available in two strengths (11:g, and 44:g per vial), as a lyophilized sterile powder. It is accompanied by diluent (0.9% NaCl in Water for Injection) in 2mL ampoules. Both lyophilized strengths are supplied in cartons of 1 vial of drug and 1 x 2mL ampoule of diluent, 3 vials of drug and 3 x 2mL ampoules of diluent, and 12 vials of drug and 12 x 2mL ampoules of diluent.
Rebif® is also available as a liquid formulation, in pre-filled syringes. Three package strengths are available: 8.8 µg/0.2mL, 22:g /0.5mL and 44:g /0.5mL. The pre-filled syringes are supplied as single units, 3-packs and 12-packs. The pre-filled syringes are ready for subcutaneous use only.
Initiation packs are available for the initial 4 weeks of treatment (see DOSAGE AND ADMINISTRATION). The initiation pack contains six syringes of 8.8 µg/0.2 mL and six syringes of 22 µg/0.5mL.
The route of administration for Relapsing forms of Multiple Sclerosis is subcutaneous. The route of administration for condyloma acuminatum is intra- and peri-lesional.
INFORMATION FOR THE PATIENT
ADMINISTRATION INFORMATION FOR THE REBIF® PATIENT
Your doctor has prescribed Rebif® treatment for relapsing forms of Multiple Sclerosis. As with any prescription medication, there are things you need to know about your treatment and what you can expect from it. The following is important patient information about how to administer Rebif®, and how to get more information should you have questions. It is recommended that the Rebif® syringe be used with Rebiject™, as some patients may find autoinjectors easier to administer.
This information relates only to the use of Rebif® in the treatment of relapsing forms of Multiple Sclerosis. If you have been prescribed any MS treatment other than Rebif®, or if you have been prescribed Rebif® for the treatment of any other condition, these instructions will not apply.
Like all medicines, Rebif® can have side effects. Interferon beta may cause flu-like symptoms such as headache, fever, chills, muscle and joint pains, fatigue and nausea. These effects are usually mild, are more common at the start of the treatment and decrease with continued use. If any of these undesirable effects are severe or persist, you should contact your physician.
Your physician may then prescribe you a pain reliever or may temporarily change your dose.
Injection site reactions including redness, swelling, discoloration, inflammation, pain, skin breakdown and tissue destruction (necrosis), may occur. The occurrence of injection site reactions usually decreases over time. Should you develop multiple lesions and/or experience any break in the skin, which may be associated with swelling or drainage of fluid from the injection site, you should consult your physician, as a decision may be required to discontinue Rebif® until healing has occurred
You should not stop or alter the medication without your doctor’s advice.
Other less common adverse events reported in association with interferon beta include diarrhoea, loss of appetite, vomiting, inflammation of the liver, sleeping difficulty, dizziness, nervousness, itching, rash, nettle-rash, hair loss, dilatation of the blood vessels and palpitation.
Certain laboratory tests may change: the number of white blood cells or platelets may decrease and liver function tests may be disturbed. These changes are generally not noticed by the patient (no symptoms), are usually reversible and mild, and most often do not require particular treatment. However, if you experience symptoms suggesting a liver disorder, such as loss of appetite accompanied by other symptoms such as nausea, vomiting, jaundice, please contact your physician immediately.
Interferons may cause your thyroid gland to function either excessively, or insufficiently. These changes in the thyroid activity are almost always not felt by the patient as symptoms, however your doctor may recommend testing as appropriate.
Depression may occur in patients with multiple sclerosis. If you feel depressed, please contact your physician immediately. If you notice any side effects not mentioned in this leaflet, please inform your doctor or pharmacist.
NOTE: Rebif® is available in two formats:ready to inject, pre-filled syringes; and lyophilized powder in vials for reconstitution prior to injection.
Be sure to follow the instructions for the Rebif® format prescribed for you.
When using Rebif® always follow the basic principles of injection:
- Maintain sterile conditions
- Check medication
- Check expiry date
- Check dosage and instructions
- Be on "safety alert"
- Rotate injection sites
The Six Steps of Rebif® Subcutaneous -Injection of Prefilled Syringes
Important: Store all injection materials and your Rebif® out of the reach of children at all times.
STEP 1: Cleanse.
Before you start, wash your hands well with soap and water. It is important that your hands and the items you use be as clean as possible. Needles should not touch any surface except alcohol-cleaned skin; keep them capped prior to use. Make sure you use a new syringe each time you inject to avoid contamination. Dispose of all syringes in the disposal container that comes with your kit.
STEP 2: Assembly of injection materials
Find a clean area and lay out everything you will need (alcohol swabs pre-filled syringe, disposal container). The injection can be given in any room where you feel comfortable. If you use your kitchen, ensure that all medicines and needles are kept well away from food.
STEP 3: Selecting and preparing the injection site
Rebif® is injected just under the skin, in the layer of subcutaneous tissue. For your own comfort, you should avoid injecting into the same area too often. There are many possible injection sites on your body (e.g., arms, thighs, buttocks, abdomen) – refer to the diagram following these instruction or in your patient diary . It is difficult to self-inject into the back of the arm, you will likely require assistance if you choose this site. It is a good idea to plan an injection site rotation schedule and note it in a diary.
Note: Do not inject in any area in which you feel lumps, firm knots or pain. Consult your doctor or healthcare professional about any such abnormalities you find.
Use an alcohol swab to clean the skin at the selected injection site. Let the skin dry completely (15 to 20 seconds) to avoid possible burning, then discard the alcohol swab.
Optional: Autoinjector
If you have been given an autoinjector, you should follow the detailed instructions that are supplied with the unit.
STEP 4: Preparing the Rebif® injection
Remove the Rebif® syringe from the blister pack by peeling back the paper covering from the arrowed end, and lifting the syringe by the barrel. DO NOT ATTEMPT TO PRESS THE SYRINGE OUT THROUGH THE PAPER FROM BELOW: this may damage the needle. Keep the needle cap on.
Carefully inspect the contents of the syringe . The liquid should be clear to slightly yellow. Do not use if the liquid is cloudy, discoloured, or contains particles. Do not worry if there are small bubbles remaining in the solution, because injecting them subcutaneously (that is, just under the surface of the skin) will do no harm.
STEP 5: Injection Rebif® subcutaneously
Your doctor or nurse will have already advised you where to inject (e.g., abdomen, front of thigh, back of arm, buttock). Refer to the injection sites diagram (keeping a diary of injection sites as they are used is recommended). Follow the detailed instructions below each time you inject Rebif® pre-filled syringes. If you have questions about injecting Rebif®, contact your healthcare professional or call Multiple Support at 1-888-MS-REBIF (1-888-677-3243).
Note: Your first Rebif® injection should be done under the supervision of your doctor or an appropriately qualified healthcare professional.
Carefully remove the cap from the needle as follows:
- Hold the syringe vertically with the needle cap pointing upwards.
- Hold the syringe with the 4 fingers of the dominant hand (the one you write with) curled round the barrel and use the thumbnail to loosen the needle cap by lifting from under the lip of the needle cap.
- Lift the needle cap completely off the needle with a continuous vertical motion, so as not to bend the needle or touch the point.
Note: If the needle is visually bent on removing the cap, DO NOT ATTEMPT TO STRAIGHTEN, as doing so could result in contamination and/or a painful injection. If the needle is bent, dispose and use a new pre-filled syringe for your injection.
- Hold the syringe like a pencil or dart.
With your other hand, gently pinch the skin around the injection site to lift it up a bit. • Resting your wrist on the skin near the site, use a quick, firm motion to insert
the needle straight into the skin at a 90° angle.
- Inject Rebif® by gently pushing the plunger all the way down. Take as much time as you need to inject all of the solution.
- Remove the needle from the skin and gently massage the injection site with a dry cotton ball or gauze.
Discard the used syringe, needle cap and cotton ball or gauze
in the disposal unit.
STEP 6: Disposal of used items
Once you have finished your injection, immediately discard the needle in the disposal container provided. When the disposal container is full, consult your clinic for the safe disposal of its contents. They should not be disposed of in household garbage.
The Six Steps of Rebif® Subcutaneous Injection of Lyophilized Powder for Reconstitution and Injection
Important: Store all injection materials and your Rebif® out of the reach of children at all times.
Note: We strongly recommend that your first Rebif® injection be done with the supervision of your doctor or an appropriately qualified healthcare professional.
STEP 1: Cleanse
Before you start, wash your hands well with soap and water. It is important that your hands and the items you use be as clean as possible. Needles should not touch any surface except cleaned skin; keep them capped prior to use. Make sure you use a new syringe each time you inject to avoid contamination. Dispose of all syringes in the disposal container that comes with your kit. STEP 2: Assembly of Injection Materials
Assemble everything you need for your Rebif® injection: clear a clean area (counter top or table) and lay your injection materials out. For each Rebif® injection, you will need:
- alcohol swabs [optional];
- one ampoule of diluent;
- one vial of Rebif®;
- one 3cc syringe with needle used for mixing;
- one 27 gauge subcutaneous injection needle; and
- your syringe and needle disposal unit (e.g. Vacutainer™, Sharps™ container).
STEP 3: Reconstituting Rebif® and Preparing the Injection
Opening the ampoule of diluent: On the neck of the ampoule, you will see a small coloured dot. Directly below this dot, the glass has been treated to make it easier to break. Gently tap the tip of the ampoule to make sure all the liquid is in the bottom. Then, holding the ampoule in one hand, place the thumb of your other hand on the ampoule neck, just above the coloured dot, and with your second or third finger on the opposite side of the neck (away from the coloured dot), press firmly to snap the ampoule top off, away from the coloured dot. Carefully place the open ampoule upright on your work surface. Discard the ampoule top in the disposal container.
Drawing up the diluent: Unwrap the 3cc syringe. Remove the needle cap and discard. With the syringe in one hand, pick up the open ampoule, insert the syringe needle into the ampoule and draw the required amount of diluent (see reconstitution table) into the syringe by pulling back the syringe plunger. Carefully set the filled syringe down on the work surface, taking care not to touch the needle or let the needle touch the work surface. Discard the empty glass ampoule in the disposal container.
| Strength | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration/mL |
| 8.8 µg | 0.2 mL | 0.2 mL | 44 µg |
| 11µg | 0.5 mL | 0.5 mL | 22µg |
| 44µg | 0.5 mL | 0.5 mL | 88µg |
Rebif® Reconstitution Table
Reconstituting Rebif®: Remove the protective aluminum cap from the vial of Rebif® powder. Pick up the syringe of diluent. Hold the Rebif® vial firmly on the work surface and slowly insert the needle of the syringe containing the diluent straight through the vial’s rubber stopper. Slowly push the syringe plunger all the way down so that all of the diluent is emptied into the Rebif® vial. Keeping the needle in the vial, wait until the powder is completely dissolved in the diluent (one minute should be sufficient). You may pick the vial up and swirl it gently - do not shake. When completely dissolved, the Rebif® solution may be yellowish in colour: this is normal.
Turn the vial of Rebif® solution upside down (with the syringe still in place). Making sure the needle tip stays in the Rebif® solution, pull the plunger back to draw the Rebif® solution into the syringe. Pull the needle back out of the vial. Discard the empty Rebif® vial in the disposal container. Unscrew the mixing needle from the syringe and discard the needle in the disposal container. Set the syringe down on the work surface.
Preparing the Rebif® subcutaneous injection. Unwrap the 27 gauge subcutaneous injection needle and screw it onto the syringe. Remove the cap from the needle and set it on the work surface. If you see any air bubbles in the syringe, hold the syringe with the needle pointing straight up. Gently tap the syringe until the air collects at the top. Carefully push the plunger in until the air bubbles are gone. Do not worry if small bubbles remain in the solution, because injecting them subcutaneously (that is, just under the surface of the skin) will do no harm.
STEP 4: Selecting the Injection Site
Rebif® is injected just under the skin, in the layer of subcutaneous tissue. For your own comfort, you should avoid injecting into the same area too often. There are many possible injection sites on your body (e.g., arms, thighs, buttocks, abdomen) -- refer to the diagram in your patient diary. It is difficult to self-inject into the back of the arm; you will likely require assistance if you choose this site. It is a good idea to plan an injection site rotation schedule and note it in a diary.
Note: Do not use any areas in which you feel lumps, firm knots, or pain; talk to your doctor or healthcare professional about any such abnormalities you find.
Optional: Autoinjector
If you have been given an autoinjector, you should follow the detailed instructions that are supplied with the unit.
STEP 5: Preparing the Injection Site and Injecting Rebif® subcutaneously
Your doctor or nurse will have already advised you where to inject (e.g., abdomen, front of thigh, back of arm, buttock). Refer to the injection sites diagram in your patient diary (keeping a diary of injection sites as they are used is recommended). Follow the detailed instructions below each time you inject Rebif®. If you have questions about injecting Rebif®, contact your healthcare professional or call Multiple Support at 1-888-MS-REBIF (1-888-677-3243).
Note: Your first Rebif® injection should be done under the supervision of your doctor or an appropriately qualified healthcare professional.
- If you chose to use an alcohol swab to clean the skin at the selected injection site, let the skin dry completely (15 to 20 seconds) to avoid possible burning, then discard the alcohol swab.
- Pick up the syringe and uncap the needle. Hold the syringe like a pencil or dart. • With your other hand, gently pinch the skin around the injection site to lift it up a bit. • Resting your wrist on the skin near the site, use a quick, firm motion to insert the needle straight into the skin at a 90° angle.
- Inject Rebif® by gently pushing the plunger all the way down. Take as much time as you need to inject all of the solution.
- Remove the needle from the skin and gently massage the injection site with a dry cotton ball or gauze.
- Discard the used syringe, needle cap and alcohol swab (if applicable)in the disposal unit. STEP 6: Disposal of used items
Once you have finished your injection, immediately discard the needle in the disposal container provided. When the disposal container is full, consult your clinic for the safe disposal of its contents. They should not be disposed of in household garbage.
Possible Sites for Injection Rebif®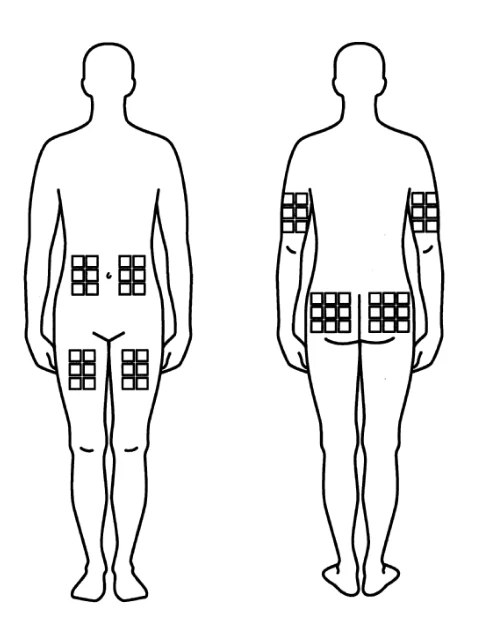
Some additional advice...
It is important that you are familiar with the correct injection technique as outlined in these instructions before beginning your treatment with Rebif®.
If the injection site bleeds afterwards, firmly press a cotton ball or gauze over the injection site immediately after removing the needle. This usually stops any further bleeding.
Local skin reactions are less likely to occur if you vary the injection site. If they do occur, they usually will disappear within a few days. In the meantime, icing the area may help reduce irritation. Swelling and irritation at the injection site may also be reduced by gently massaging the area for five minutes after the injection has been given. If a generalized rash develops, you should always report it to your doctor or nurse. Bruises may also occasionally occur at the injection site -- even when the injection has been given correctly -- but they will disappear.
Finally, remember that every treatment is individualized. Yours has been carefully designed for you by your doctor according to your own specific needs. It is very important that you keep your appointments and follow your doctor's instructions, particularly with regard to the amount and frequency of the medication you are taking. If you forget or miss an injection, do not panic, but you should consult your doctor or nurse for advice.
Rebif® syringes may be stored for limited period (while travelling or where a refrigerator is not available, etc…) at room temperature (up to 25ºC), but not more than 1 month.
Serono Canada Inc., Mississauga, Ontario, Canada L5K 2N6 ®Trademark ©2003
If you have any questions, call
Multiple Support 1-888-MS-REBIF (1-888-677-3243).
PHARMACOLOGY
ANIMAL PHARMACOLOGY
Animal Pharmacodynamics: A study of the cardiovascular and respiratory effects of Rebif® (Interferon beta-1a) has been carried out in a conventional anaesthetized, instrumented model in the rat. Bolus IV doses up to 11:g /kg showed no effects on cardiac function, ECG, blood pressure or respiration.
Rebif® has been tested in toxicology studies up to 3 months in duration in rats and up to 6 months in monkeys. No toxicities except for transient pyrexia were observed.
Acute and repeated dose toxicity studies in rat and cynomolgus monkey showing that doses up to 73:g/kg IV or IM did not produce clinical signs of dysfunction of the nervous system, gastrointestinal tract and smooth muscle, or dysfunction of their physiological control. These acute experiments also showed that Rebif® 73:g /kg IV and IM caused transient pyrexia (in monkeys, this also occurred in the 13-week study at Rebif® doses of 0.25 - 3.67:g /kg IV).
Animal Pharmacokinetics: The single dose kinetics of Rebif® has been examined in the rat and monkey to validate their use in toxicity tests as a model for man. The outcome of these studies is confirmed by the comparability of the findings with the results of single dose studies of other hIFN-betas, and the information gained from them about kinetics after multiple dosing. Absorption from an SC or IM site is rapid, the bioavailability is about 30-40% and some circulating IFN-beta persists up to 24 hours in the cynomolgus monkey dosed SC. Slight accumulation occurred after twice daily SC or IM dosing.
HUMAN PHARMACOLOGY
Human Pharmacokinetics: In a randomized, double-blind, placebo-controlled, cross-over study, 12 healthy volunteers were injected with a single dose of 22:g Rebif® by the IV, IM or SC route. The pharmacokinetic analysis showed that 22:g Rebif® administered by the IV route follows a two-compartment model with a short distribution half-life of approximately 5 minutes and an elimination half-life of about 5h, (similar results have also been reported for IFN-beta-1b). Following IM or SC administration, Rebif® showed a rather flat plasma concentration/time curve, (similar to the data obtained in rats and monkeys), with an absolute bioavailability of about 15%.
The bioavailability of human interferon beta following single-dose subcutaneous and intramuscular administration of recombinant human interferon beta-1a was compared.
The pharmacokinetic parameters showed a high intersubject variability, but intramuscular and subcutaneous routes of administration demonstrated equivalent bioavailability.
Human Pharmacodynamics: 2'-5'-oligoadenylate synthetase is an enzyme shown to be produced in response to exposure to IFN both in vitro and in vivo. In the above mentioned randomized study, it was found to increase following Rebif® administration, however, the mean peak elevation was independent of the route of administration. The increase in (2-5A) synthetase levels was maximal at 24h (earlier samples were not collected) and levels were still significantly elevated 72h after Rebif® injection.
In a second randomized, double-blind, placebo-controlled study comparing the safety and pharmacodynamics of a single IM dose of 22:g of IFN-beta-1a (Rebif®) vs. 6 MIU of native-IFN-beta (Frone™) in 12 healthy volunteers, changes in (2-5 A) synthetase, p78 (the human Mx protein) and neopterin were followed Significant rises in serum (2-5 A) synthetase, p78 and neopterin levels were observed in both groups. There were no significant differences seen in these responses, between fibroblast-derived IFN-beta and r-hIFN-beta.
The effects of Rebif® were also compared to those of Frone™ both administered as a single injection of 22:g by the IV route in a cross-over, randomized, double-blind, placebo-controlled study in 12 healthy volunteers. Serum neopterin and beta2-microglobulin levels, as well as intracellular (2-5 A) synthetase and p78 protein synthesis, increased significantly after the injection of both drugs, (respectively at 24h for the serum markers, and between 24h and 48h for the intracellular markers), showing very similar profiles.
Previous work has shown these biomarkers to be of value in assessing the pharmacodynamics of interferons, but the relationship between serum IFN-beta concentration, measurable pharmacodynamic response and the mechanism(s) by which Rebif® exerts therapeutic effects in multiple sclerosis remains essentially unknown.
Additional studies investigated the importance of increased frequency of administration. The results confirmed that more frequent administration (i.e., three times per week vs. once per week) elicits the optimal pharmacologic response.
Special Tolerance Studies in Human: In an open-label study in patients with malignant diseases unresponsive to standard therapies, Rebif® (Interferon beta-1a) was given as a bolus IV injection on day 1, followed one week later by daily subcutaneous injections for 28 consecutive days at the following dose levels: 5.5, 11, 22, 44, 66 or 88:g /m2. Preliminary results indicate that the maximum tolerated dose is probably 44:g /m2.
Clinical Summary
Multiple Sclerosis
Rebif® has been tested in four large, well-controlled studies of 1900 patients with 1200 on active therapy.
PRISMS STUDY (Prevention of Relapses and Disability by Interferon β-1a Subcutaneously in relapsing-remitting Multiple Sclerosis)
A total of 560 patients diagnosed with clinically definite or laboratory-supported relapsing-remitting multiple sclerosis EDSS 0-5 with at least a 1-year history before study entry and a history of 2 or more acute exacerbations in the 2 years prior to study entry were enrolled and randomized to 3 treatments (placebo, 22:g Rebif®, or 44:g Rebif®) in a ratio of 1:1:1. About 90% of patients completed the 2 years of treatment, and entered the extension phase: 167 from the original 44 µg tiw group, 167 from the original 22 µg tiw group, and 172 from the original placebo group. Prior to the start of the extension phase and without knowledge of study results, all patients from the original placebo group were re-randomised to receive either 22 or 44 µg tiw (85 randomised to 22µg, and 87 randomised to 44µg). The patients from the original 22 and 44 µg tiw groups continued their treatment as originally randomised. Of the original 560 patients enrolled in the study, 445 (79%) remained in the study to the end of year 4. Less than 10 % of patients treated with active therapy with drew for adverse events over 4 years.
Rebif® 66µg weekly (22µg, 3x/week) and 132µg weekly (44 µg, 3x/week) had a significant effect on the primary outcome measure by reducing relapse count compared to placebo. The relapse rate reduction continued during years 3 and 4 of therapy. Patients converting to Rebif® from placebo demonstrated a 52-53% reduction in relapse rate compared to years on placebo. Over 4 years, Rebif® 132µg weekly was superior to Rebif® 66µg weekly in reducing relapses and although this difference did not achieve statistical significance (p= 0.069), neither was the study powered to demonstrate a significant difference between two active treatment arms. Rebif® 132µg weekly reduced the time to onset of progression of disability by 18 months compared to placebo crossover patients. High dose Rebif also reduced the number of EDSS 1-point changes made by a patient compared to placebo and compared to Rebif® 66µg weekly. Both doses strongly diminished the MRI active lesion development and the accumulation of lesion burden over time compared to placebo. Rebif® 132µg weekly was significantly more effective on MRI outcomes than Rebif® 66µg weekly. These data demonstrate a continued benefit of Rebif® therapy up to 4 years and provide further evidence of a dose-effect relationship in MS. Whereas after two years of therapy, there had been a consistent trend in favour of the high dose which was statistically significant for MRI active lesions, further observation to 4 years showed that these trends continued and for the majority of endpoints became statistically significant. Finally, patients treated early (study start) attained more benefit at 4 years than those delaying treatment until the start of year 3.
Exacerbation rate during Years 1-4 : ITT (Intent to treat)
| Time Period | Estimated annual exacerbation rate | ||
| Placebo/Rebif® (n=187) | Rebif® 66µg weekly (n=189) | Rebif® 132µg weekly (n=184) | |
| Years 1-4 | 1.02 | 0.80 | 0.72 |
| Treatment comparison | p-value* | ||
| Years 1-4 | Rebif® 132µg vs. placebo/Rebif® Rebif® 66µg vs. placebo/Rebif® Rebif® 66µg vs. Rebif® 132µg | 0.0001 0.0001 0.069 | |
*Poisson Regression model with effects for treatment and center and treatment by center interaction
Exacerbation count during years 1-2 and years 3-4 (all patients treated with placebo during years 1-2 (placebo switch patients))
| Time period | Statistics | Placebo/Rebif® 66µg weekly (n=85) | Placebo/Rebif® 132µg weekly (n=87) |
| Years 1-2 | Mean (SD) Median Range | 2.60 (2.11) 2 (0.00, 10.00) | 2.57 (1.99) 2 (0.00, 8.00) |
| Years 3-4 | Mean (SD) Median Range | 1.21 (1.55) 1 (0.00, 9.00) | 1.23 (1.24) 1 (0.00, 6.00) |
| Change from Years 1-2 to Years 3-4 | Mean (SD) Median Range p-value* | -1.39 (2.47) -1 (-10.00, 9.00) 0.0001 | -1.34 (1.85) -1 (-6.00, 2.00) 0.0001 |
*p-value from Wilcoxon Signed-Rank test Proportion of exacerbation-free patients at the end of year 4 : ITT
| Time Period | Number and proportion of exacerbation-free patients | ||
| Placebo/Rebif® n/N* (%) | Rebif® 66µg weekly n/N* (%) | Rebif® 132µg weekly n/N* (%) | |
| Year 4 | 12/180 (6.67) | 26/181 (14.36) | 34/179 (18.99) |
| Treatment comparison | p-value# | ||
| Year 4 | Rebif® 132µg vs. placebo/Rebif® Rebif® 66µg vs. placebo/Rebif® Rebif® 66µg vs. Rebif® 132µg | 0.0002 0.0158 0.0159 | |
*Exclude patients lost to follow-up without any exacerbation count # p-value is from a logistic regression model with effects for treatment and center.
Time to first exacerbation (from 2 year database)
| Placebo | Rebif® 66:g/ week 132:g/ week | p-value | |||
| Efficacy parameters | Rebif® 66:g/wk vs Placebo | Rebif® 132:g/wk vs Placebo | |||
| Median time to first exacerbation (months) | 4.5 | 7.6 | 9.6 | 0.0008 | <0.0001 |
Time to second exacerbation (from 4 year database) and proportion with second relapses: ITT years 1-4
| Time Period | Time to second exacerbation | Placebo/ Rebif® N = 187 | Rebif® 66µg weekly n=189 | Rebif® 132µg weekly n=184 |
| Years 1-4 | First quartile in days (months) Median in days (months) | 216 (7.1) 449 (14.8) | 329 (10.8) 702 (23.1) | 359 (11.8) 965 (31.7) |
| Treatment comparison | p-value# | |||
| Years 1-4 | Rebif® 132µg vs. placebo Rebif® 66µg vs. placebo Rebif® 132µg vs. Rebif® 66µg | 0.0001 0.0058 0.0460 | ||
The first quartile and median time to second exacerbation are Kaplan-Meier estimates. #p-value is from a Cox proportional hazards model with effects for treatment and center. Time to Confirmed Progression in Disability: Kaplan-Meier Curves by 3-Treatment Group
Key Placebo/Treatment
Rebif 22 mcg tiw Rebif 44 mcg tiw
0.4
0.6
0.8
1.0
Months 0 6 12 18 24 30 36 42 48 Proportion
of
Progression
Free
Patients
Time to progression for the ITT group shows that Rebif® 132µg weekly compared to placebo/treatment has a significant prolongation of the time to progression (p=0.047). This prolongation is 18 months for Rebif® 132µg weekly and 12 months for Rebif® 66µg weekly. There was no significant difference between the 132µg/week dose and the 66µg/week dose in the time to confirmed progression (p=0.333). Only the 132µg/week dose was effective at reducing the time to confirmed EDSS progression in the ITT analysis. The time to first confirmed progression did not differ significantly between the 66µg/week dose and the placebo crossover ITT group (p=0.289).
Proportion of progression-free patients at the end of Year 4: ITT
| Nu | mber and proportion of progression free patients | ||
Time Period Pla n/N | cebo/Rebif® (%) | Rebif® 66µg weekly n/N (%) | Rebif® 132µg weekly n/N (%) |
| Year 4 74/ | 161 (46%) | 88/173 (51%) | 92/164 (56%) |
| Tre | atment comparison | p-value# | |
Year 4 Reb Reb Reb | if® 132µg vs. placebo/Rebif® if® 66µg vs. placebo/Rebif® if® 132µg vs. Rebif® 66µg | 0.0702 0.4101 0.3090 | |
Excludes patients lost to follow-up without any confirmed progression. *p-value is from a logistic regression model with effects for treatment and center. Number of confirmed EDSS changes during Years 1-4: ITT
| Estimated confirmed annual progression rate * | |||
| Time Period | Placebo/Rebif® n=187 | Rebif® 66µg weekly n=189 | Rebif® 132µg weekly n=184 |
| Years 1-4 | 0.24 | 0.22 | 0.17 |
| Treatment comparison | p-value# | ||
| Years 1- 4 | Rebif® 132µg vs. placebo/Rebif® Rebif® 66µg vs. placebo/Rebif® Rebif® 132µg vs. Rebif® 66µg | 0.0048 0.5227 0.0295 | |
* from a Poisson regression model with effects for treatment and center.
Effect on MRI scans in multiple sclerosis
The MRI data show a highly significant effect of interferon therapy on BOD (burden of disease) and MRI activity measures, a highly significant dose effect on both BOD and MRI activity measures for patients treated with 132µg weekly vs. 66µg weekly after 4 years (p=0.009 and p<0.0001 respectively), an overall net reduction in BOD of 6.2% over 4 years in patients treated with 132µg weekly, and that patients originally treated with the high dose of Rebif® retain an overall significant benefit on BOD and activity measures compared to patients treated with placebo followed by 132µg weekly for two years (p=0.003).
Percent change in burden of disease during Years 1-4- 4-treatment groups
| Time period | Statistics | Placebo / Rebif® 66 µg weekly | Placebo / Rebif® 132 µg weekly | Rebif® 66:g/week | Rebif® 132:g/week |
| Years 1-4 | N Mean (SD) Median Range | 57 16.3 (31.0) 9.7 (-24.9, 151.5) | 49 13.0 (31.0) 7.2 (-31.7, 124.6) | 117 20.4 (71.3) 3.4 (-64.1, 351.0) | 111 2.4 (34.5) -6.2 (-53.1, 188.1) |
| Time period | Treatment comparison | p-value* | |||
Years 1-4 Rebif® 132µg vs. placebo/Rebif® 132µg
Rebif® 66µg vs. placebo/Rebif® 66µg Rebif® 132µg vs. Rebif® 66µg
0.0027 0.1125 0.0089 *p-value from an ANCOVA on ranks with effects for treatment and center adjusting for baseline burden of disease
Mean Number of T2 Active Lesions per Patient per Scan During Years 1-4 and 3-4: 4-Treatment Groups
| Time Period | Statistics | Treatment Group | |||
Placebo/Rebif® 22 mg tiw | Placebo/ Rebif® 44 µg tiw | Rebif® 22 µg tiw | Rebif® 44µg tiw | ||
| Years 1-4 | N Mean (SD) Median Range | 90 4.0 (4.9) 2.0 (0.0, 26.5) | 92 4.0 (4.0) 2.7 (0.0, 19.0) | 180 2.6 (4.0) 1.3 (0.0, 22.3) | 180 1.5 (3.3) 0.5 (0.0, 27.5) |
| Years 3-4 | n Mean (SD) Median Range | 80 2.0 (3.3) 0.5 (0.0, 19.5) | 75 1.8 (2.8) 1.0 (0.0, 12.0) | 161 2.1 (3.5) 1.0 (0.0, 19.0) | 150 1.2 (3.3) 0.0 (0.0, 23.5) |
| Time Period | Treatment Comparison | p-value (a) | |||
| Years 1-4 | Rebif® 44µg tiw vs Placebo/Rebif® 44µg tiw Rebif® 22µg tiw vs Placebo/ Rebif® 22µg tiw Rebif® 44µg tiw vs Rebif® 22µg tiw | < 0.0001 0.0009 <0.0001 | |||
| Years 3-4 | Rebif® 44µg tiw vs Placebo/Rebif® 44µg tiw Rebif® 22µg tiw vs Placebo/ Rebif® 22µg tiw Rebif® 44µg tiw vs Rebif® 22µg tiw | 0.0007 0.8006 <0.0001 | |||
(a) p-value from and ANOVA on ranks with effects for treatment and center
Requirement for steroids: During the first two years, the proportion of patients requiring steroids for MS(excluding non-MS indications) was higher in the placebo group (more than 50%) than in either of the 2 Rebif® groups (around 40% in each group). For patients on therapy for 4 years, the majority (76.4%) of steroid courses were for MS indications and over 90% of MS-related courses were for the treatment of exacerbations. Comparison of the rate of steroid use for actively treated patients over years 1-4 indicates a significantly lower rate in the 132µg weekly group compared with the 66 µg weekly group (p = 0.032), providing supportive evidence of a dose-effect relationship for interferon therapy in MS.
Hospitalisation for multiple sclerosis: During the first two years, the observed mean number of hospitalisations for MS in the Rebif® 66 and 132µg weekly groups represented reductions of 21% and 48%, respectively, from that in the placebo group. The number of hospitalisations per patient was 0.48 for placebo, 0.38 for 22mcg tiw and 0.25 for 44mcg tiw. Only the difference between 44mcg tiw and placebo was statistically significant (p=0.038)After four years on study, comparison of the hospitalisation rates was performed on only the two groups receiving active therapy during years 1-4. It revealed no significant difference between groups with a mean value of 0.2 (median = 0) and 0.1 (median = 0) hospitalisations/patient/year for 66 and 132µg groups, respectively. The lack of significant difference could in part be due to the low number of events overall even though the rate of 66µg is double that of 132µg..
OWIMS STUDY (Once Weekly Interferon beta-1a for Multiple Sclerosis)
A total of 293 patients diagnosed with clinically definite or laboratory-supported relapsing MS with at least a one-year history, one or more exacerbations in the previous two years, 3 or more lesions on MRI at the pre-study scan, and an EDSS between 0 and 5.0 were enrolled and randomized to the 3 treatments (placebo, 22µg Rebif®, or 44µg Rebif®) in a ratio of 1:1:1. The patients were treated once weekly by subcutaneous injection. About 92% of patients completed 48 weeks, and very few patients withdrew from the study due to adverse events.
MRI as a measure of MS activity was evaluated in two ways: number of active lesions on T2-weighted and T1-weighted gadolinium enhanced MRI scans at Weeks 4, 8, 12, 16, 20 and 24 during treatment (and compared to baseline) and the burden of disease evaluated in all patients using the T2-weighted sequence at the same time points. Further T2-weighted MRIs were conducted at Weeks 48 and 96.
MRI disease activity
A non-significant decrease compared with placebo in combined active lesions per patient per scan was noted for the 22µg QW dose (29.6%), and a modest yet significant reduction was apparent with the 44µg QW dose (53.5%). A dose-effect was also noted in other MRI parameters: the percentage of MRI scans showing combined active lesions was 50%, 45% and 33% for placebo, Rebif® 22µg QW and Rebif® 44µg QW (not statistically significant). Only the highest dose of Rebif was associated with a significant reduction in the proportion of active scans (p=0.02), T2 active lesions alone and T1-Gd enhancing lesions alone (p<0.01) as compared to placebo. MRI disease burden
Over 1 year of treatment, the change from baseline in burden of disease (total PD/T2 lesion area) differed significantly between both active treatment groups and placebo. Burden of disease increased from baseline in the placebo groups and decreased in the active treatment groups, (decreased by 2.0% and 1.4% for Rebif® 22µg and 44µg QW, respectively, and no statistical difference was seen between the two groups).
Exacerbation frequency
No reduction was evident with the 22µg QW dose, and a 19% reduction was seen with the 44µg QW dose, a difference that did not reach statistical significance (p=0.21), although the study was not powered for this outcome.
Conclusion
While some modest MRI effect was seen, no significant clinical benefit was seen over the one-year study duration. This study suggests that once weekly administration at doses of 22 or 44mcg does not provide significant benefit in established RRMS.
SPECTRIMS STUDY (Secondary Progressive Efficacy Clinical Trial of RecombinantInterferon beta-1a (Serono) in Multiple Sclerosis)
SPECTRIMS was a large randomised, double-blind, placebo-controlled three-year study performed to examine the effects of Rebif® on key outcome parameters in a patient population with more advanced multiple sclerosis disease.
SPECTRIMS was conducted in 22 centres in Europe, Canada, and Australia. A total of 618 patients (229 men and 389 women) aged 18-55 years with secondary progressive MS (EDSS 3-6.5) were randomised to receive Rebif® 66µg weekly(22 µg, 3x/week), 132µg weekly (44 µg, 3x/week) or matching placebo as SC injections for 3 years. To reduce the occurrence of anticipated side effects, the dose was increased gradually: 20% of the assigned dose was given for two to four weeks, then 50% for two to four weeks, and the full dose thereafter.
The primary efficacy endpoint was the effect of treatment on the deterioration of disability. The deterioration of disability was prospectively defined as the time to progression in disability by at least 1.0 point on the EDSS, or a deterioration of 0.5 point if the baseline EDSS was $ 5.5, confirmed at two consecutive visits three months apart. Secondary outcome measures included relapse count, MS lesion activity measures on MRI and the change in total MRI lesion burden. Several tertiary outcome measures were also evaluated.
A total of 571 patients (92.4%) completed the 3-year study, with 96.5% of all possible data collected. The proportions of patients completing were similar in the placebo (90.7%), Rebif® 66 µg (93.3%), and Rebif® 132 µg (93.1%) groups. Of the 112 patients who discontinued prematurely, only 47 (7.6% of the overall population) were lost to follow-up. All analyses were based on intent-to-treat principles.
Clinical endpoints
The primary outcome measure was time to confirmed progression in disability, with the main comparison being between Rebif® 132 µg tiw and placebo.Although a trend in favour of therapy was noted for the primary outcome, this difference was not statistically significant (p=0.146). An unexpected treatment by sex interaction was noted (p=0.035) which clouds interpretation.
The differential effect of treatment, based on whether or not patients had relapses during the 2 years before entry to the study, was also examined. After the sex-treatment interaction was identified, Serono investigated other possible baseline factors that could have possibly been related to the sex-treatment interaction. As part of this investigation, a number of clinically relevant baseline disease and demographic factors were each investigated in order to see if the sex-treatment interaction remained in the presence of these factors. As part of this process, it was noted that the number of relapses in the two years prior to the study also showed an interaction with treatment. The effect of treatment (both groups combined) on time to progression was analysed separately for “relapsing” and “non-relapsing” patients. This analysis indicated that the benefit for the combined treatment group was greater for relapsing patients (n=293) as opposed to non-relapsing patients (n=325). The hazard ratio for progression was 0.74 in the relapsing patients (p=0.055), while the hazard ratio was 1.01 in the non-relapsing patients (p=0.934). The corresponding odds ratios for proportion progressing in the treated relapsing and non-relapsing patients were 0.52 (p=0.027) and 1.07 (p =0.802), respectively.
Proportion of Patients progressing in Relapsing SPMS cohort: Combined Treatment groups compared to Placebo
0
0.1
0.2
0.3
0.4
0.5
0.6
0.7
0.8
0.9
1
0 1 2 3
Years Treated
Placebo
Secondary endpoints
The three secondary endpoints were exacerbation count per patient, MRI activity and burden of disease.
Table 1. Secondary endpoints results
| Placebo | Rebif® 66 µg | Rebif® 132 µg | P value 66 µg vs. placebo | P value 132 µg vs. placebo | |
| Exacerbation count per patient at 3 years | 2.05 ± 2.14 | 1.44 ± 1.63 | 1.46 ± 1.68 | <0.001 | <0.001 |
| Relapse Rate (number per year) | 0.71 | 0.50 | 0.50 | <0.001 | <0.001 |
| T2 Active lesions per patient per scan (median) | 0.67 | 0.20 | 0.17 | <0.0001 | <0.0001 |
| T2 New lesions per patient per scan (median) | 0.33 | 0.17 | 0.00 | <0.0001 | <0.0001 |
| T2 Newly enlarging lesions per patient per scan (median) | 0.17 | 0.00 | 0.00 | <0.0001 | <0.0001 |
| Mean % T2 active scans | 46% | 28% | 24% | <0.001 | <0.001 |
| % patients with no T2 active scans during treatment | 24% | 36% | 41% | <0.001 | <0.001 |
| % Change in BOD (median) | +10.0 | -0.5 | -1.3 | <0.001 | <0.001 |
Both doses of Rebif® conferred significant benefits, reducing the relapse rate by approximately 30% (p<0.001), reducing T2 activity by 70-75% (p<0.001), and the percentage change in BOD increased by 10% in the placebo group while decreasing by 1.3% and 0.5% in the low and high dose groups respectively (p<0.001 for both doses compared to placebo).
Allied to the T2 active lesion counts were significant effects of treatment on the proportion of active scans (66% reduction, p<0.001) and the proportion of patients who did not have any active lesions on their scans during the study (71% increase, p<0.001). The comparison of relapsing vs. non-relapsing patients revealed differences in both baseline MR characteristics and on-study behaviour and treatment response.
For the pre-study relapsing group of patients, treatment was more effective on the secondary outcome measures than for the non-relapsing sub-group, as occurred for the primary endpoint. Table 2. Summary of on-study behaviour of Relapsing vs. Non-relapsing patients
| Relapsing pre-study | Non-relapsing pre-study | ||||||
| Dose of Rebif® | 132 µg | 66 µg | Placebo | 132µg | 66µg | Placebo | |
| Total number of patients per group | 98 | 97 | 98 | 106 | 112 | 107 | |
| % progressing at the end of the study | 59 | 56 | 70 | 58 | 63 | 61 | |
| Relapse rate (number per year) | 0.67*** | 0.57*** | 1.08 | 0.36 | 0.43 | 0.39 | |
| T2 activity (median) | 0.17*** | 0.17*** | 1.17 | 0.17* | 0.20 | 0.33 | |
| % Change in BOD (median) | -1.3*** | -1.5*** | 11.8 | -1.4*** | 1.2 | 8.4 | |
***: p<0.001, **: p<0.01, *: p<0.05 compared with placebo
Tertiary endpoints
Other relapse related outcome measures including time to first relapse (p=0.032), time between first and second relapse (p=0.002), relapse severity (p=0.049), need for steroid treatment (p=0.005) and need for hospitalisation (p=0.005), were all favourably affected by Rebif® 132 µg treatment. The only relapse related measure which was not significantly affected by 132 µg therapy was relapse duration.
Composite Score
In a disorder such as MS, there are often multiple outcomes that may measure different impacts of the disease. These measures may be independent of one another but each may also be important to the overall benefit to the patient. A statistical method exists to combine these measures in one composite score. The value of this measure is that if all outcomes are favourably affected, a strong result is seen while if there are some outcomes with good effect and others without, the composite score will not show a treatment effect. In this study the five outcomes that were combined were time to progression, relapse count, T2 activity, change in BOD and IDSS (Integrated Disability Status Score). The composite score of these outcomes showed a highly significant result (p<0.001) in favour of Rebif® at both doses.
ETOMS STUDY – Early Treatment of Multiple Sclerosis
A total of 309 patients with clinically probable or laboratory supported definite MS were randomised in this clinical trial to receive either 22 mcg of Rebif® once a week by S.C. injections or matching placebo for 2 years. Patients were to have their first MS attack in the 3 months preceding study entry and have MRI scan strongly suggestive of MS. About 78% of these patients received the allocated treatment during the 2-year study period and 90% remained on study until the end of 2 years. Over 85% of patients stopping blinded study treatment did so after having their second MS attack on study. Very few patients withdrew due to adverse events.
The treatment efficacy was determined by comparing the rate of patients converting to clinically definite MS (CDMS) in the active arm versus placebo. MRI as a measure of disease activity was evaluated by the number of new T2 lesions and the proportion of patients without MRI active scans.
Conversion to CDMS
A significant reduction in the proportion of patients converting to CDMS was observed in the treated group as compared to placebo (34% versus 45% respectively; p=0.047). The time to the second relapse increased significantly from 252 days in patients treated with placebo to 569 days for patients treated with Rebif® (p=0.034). The annual relapse rate was significantly lower in the Rebif® group (0.33) as compared to the placebo group (0.43) with a p value of 0.045.
MRI disease measures
A significant decrease compared with placebo in the number of new T2 lesions was observed in patients treated with Rebif® 22 mcg once a week (median 2.0 versus 3.0 respectively; p<0.001). The proportion of patients with no MRI active scan was significantly higher in the Rebif® group (16%) than in the placebo group (6%) with a significant statistical difference (p=0.005). No difference between the study groups was observed for T1 active lesions. The total T2 lesion volume as compared to the baseline value increased of 8.8% in the placebo group while a decrease of 13% was observed in patients treated with Rebif® 22 mcg once a week; the difference being statistically significant (p=0.002).
Conclusion
This study demonstrated that 22 mcg of Rebif® injected once weekly significantly reduced the risk of a second relapse leading to the conversion to CDMS in patients with a first episode highly suggestive of MS. The clinical benefit was confirmed by a significant impact on MRI lesion activity and accumulation of disease burden.
Condyloma acuminatum
The results from four double-blind, placebo-controlled studies, including 349 patients (aged 17-62), each reveal that Rebif®, when injected intralesionally at a dose of 3.67 µg (1MIU)/lesion 3 times per week for 3 weeks, is efficacious in the treatment of condyloma acuminatum in men and women. This efficacy is evidenced by both the induction of complete disappearance of lesions as well as the reduction in the area of lesions. The majority of treated patients in these studies had recurrent warts that had failed previous treatments. The number of lesions treated per patient was between 3 and 8, as stated in the summary table below.
| Stud y | # patients/ % previously treated | # lesions treated | Treatment | Results |
| 1 | 25 / 80% | 3 | 0.12 or 3.67 µg of Rebif®/lesion, or placebo, 3 times per week for 3 weeks | Rebif® at a dose of 3.67 µg/ lesion is efficacious, as evidenced by the induction of complete disappearance of lesions and the reduction in the area of lesions. The 0.12 µg dose of Rebif® did not show advantages over placebo treatment. |
| 2 | 100 / 72% | 6 | 3.67 µg of Rebif®/ lesion, or placebo, 3 times per week for 3 weeks | There was a significant increase in Major Response rate at Month 3 in patients who received Rebif® vs. placebo (p<0.0001). The Complete Response rate at Month 3 was significantly in favor of patients who received Rebif® (p≤ 0.0162). |
| 3 | 100 / 52% | 8 | 3.67 µg of Rebif®/ lesion, or placebo, 3 times per week for 3 weeks | For the Israeli centre, the results from Week 6, supported by those from study Day 19 demonstrate the efficacy of Rebif®. Because of the study design and the non-compliance with the study protocol at the German centre, indications of efficacy were not supported by the results from the analyses where patients from both centres were pooled. |
| 4 | 124 / 72% | 6 | 3.67 µg of Rebif®/ lesion, or placebo, 3 times per week for 3 weeks | This study showed that Rebif® was effective with the proportion of patients achieving a complete or Partial Response at Day 19 and Week 6, and a significant reduction in the total area of lesions on Day 19 and Week 6. Because of the study design, the effect of Rebif® at Month 3 was not demonstrated. |
Immunogenicity: The determination of the presence of antibodies to human IFN-β was performed in all 4 studies. A total of four patients had anti beta-interferon antibodies at pre-entry, and 6 other patients had at least a positive result for total binding antibodies at some point during the study. Antibodies were of low titer, and none of the antibodies were neutralizing to human IFN-β biological activity.
TOXICOLOGY
Acute Toxicity
In formal single dose tests in the mouse and rat, Rebif® (Interferon beta-1a) doses of 37:g /kg and 73:g /kg administered by intravenous or intramuscular route showed no effects during life or at autopsy.
In a similar experiment in cynomolgus monkeys, Rebif® doses of 73:g /kg IV or IM produced only a 1-2°C rise in rectal temperature from 2 to 7 hours. No other effects were seen in the acute studies. Repeated Dose Toxicity
All these experiments have been affected by the development of neutralizing antibodies against Interferon beta-1a (and the HSA carrier protein in the formulation).
In the rat, the principal findings were of local trauma at the sites of the repeated injections and of higher titre antibodies against HSA than against Interferon beta-1a by week 4, and increasing in incidence at week 13. The experiment using the IV route was marred by a number of accidental deaths mainly due to respiratory infection probably associated with tail (injection site) damage. Injection site lesions occurred in all groups, including the control group, and may have been possibly consequent on several factors, including needle trauma and a local allergic reaction to heterologous proteins (Interferon beta-1a and/or HSA) which predisposed to local infection with daily venipuncture. The infections spread then to the lungs (bacterial emboli). The studies in the cynomolgus monkeys showed brief pyrexia on day 1 after all IV doses (0.917 :g 3.67:g /kg), which was not present subsequently. The other findings were of anti-HSA and anti Interferon beta-1a antibodies appearing by week 4, and local trauma at the injection sites in all groups, including controls. No other findings were recorded.
Genetic toxicity testing
Rebif® has been shown to be neither mutagenic nor clastogenic.
Reproduction toxicity testing
A teratology study in monkeys was performed showing that Rebif® is not teratogenic. An increased risk of abortion has been attributed to the interferons, based on observations with interferon alpha and interferon beta-1b. No information is available on the effects of the interferon beta-1a on male fertility.
REFERENCES
- 1) Paty DW, Li DKB, Oger JJ-F, et al. Magnetic resonance imaging in the evaluation of clinical trials in Multiple Sclerosis. Ann Neurol 1994; 36: S95-S96
- 2) Khoury SJ, Goottman CRG, Oral EJ, et al. Longitudinal MRI in multiple sclerosis: correlations between disability and lesion burden. Neurology 1994; 44: 2120-2124
- 3) Weinstock-Guttman B, Ransohoff RM, Kinkel RP, Rudick RA. The interferons: biological effects, mechanisms of action, and use in Multiple Sclerosis. Ann Neurol 1995; 37/1: 7-15
- 4) Liberati AM, Horisberger MA, Palmisano L, et al. Double-blind randomized phase I study on the clinical tolerance and biological effects of natural and recombinant interferon-beta. J Interferon Res 1992; 12: 329-336
- 5) McFarland HF, Frank JA, Albert PS, et al. Using gadolinium-enhanced magnetic resonance imaging lesions to monitor disease activity in Multiple Sclerosis. Ann Neurol 1992; 32: 758-766
- 6) Abdul-Ahad AK, Galazka AR, et al. Incidence of antibodies of interferon-β in patients treated with recombinant human interferon-β-1a from mammalian cells. Cytokines, Cellular & Molecular Therapy 1997; 3: 27-32.
- 7)
PRISMS Study Group: Ebers G, Paty DW, et al. Prevention of relapses and
disability by interferon-beta-1a, Rebif, subcutaneously in Multiple Sclerosis. Integrated Clinical and Statistical Report of 4-year data, 2000, Data on file.
- 8) OWIMS Study Group: Ebers G, Lee D., et al. Evidence of interferon beta-1a dose response in relapsing-remitting MS. Neurology 1999, 53: 679 – 686
- 9) SPECTRIMS Integrated Clinical and Statistical Report 1999; data on file
- 10) Lesaux J., Jadback, G. et al, Improving the convenience of home-based interferon beta-1a therapy for multiple sclerosis. Journal of Neuroscience Nursing 1999, 31: 174-179
- 11)
Oger J, and Freedman Mark, Consensus Statement of the Canadian MS Clinics Network on:
the use of disease modifying agents in multiple sclerosis. The Canadian Journal of Neurological Sciences 1999, 26, 274
- 12) Munafo A., Trinchard-Lugan I. et al, Comparative pharmacokinetics and pharmacodynamics of recombinant human interferon beta-1a after intramuscular and subcutaneous administration. European Journal of Neurology 1998, 5: 187-193
- 13) Rothuizen, LA, Buclin, T. et al, Influence of interferon beta-1a dose frequency on PBMC cytokine secretion and biological effect markers. Journal of Neuroimmunology 1999, 131-141 14) Paty DW, Hartung HP, et al. Management of relapsing-remitting multiple sclerosis: diagnosis and treatment guidelines. European Journal of Neurology, 6 (S1), 1999, pp S1-S35
- 15) Monsonego I., Trinchard-Lugan I., Roy S. et al. A randomised, double-blind, placebo-controlled, dose-comparative study of recombinant human interferon-beta administered by the intralesional route in the treatment of condyloma acuminatum. 11th Papillomavirus Workshop, Edinburgh, Scotland, 5th-11th September 1992, Abstract 214.
- 16)
Patten, S.B and Metz, L.M. Interferon beta-1a and depression in secondary progression MS:
Data from the SPECTRIMS Trial. Neurology 2002; 59: 774-746.
- 17) Patten, S.B. and Metz, L.M. Interferon beta-1a and depression in relapsing-remitting multiple sclerosis: an analysis of depression data from the PRISM clinical trial. Multiple Sclerosis 2001; 7: 243-248.