


Product Monograph - Reddy-Progesterone
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.1 Pediatrics, 1.2 Geriatrics | 02/2026 |
|---|---|
| 2 CONTRAINDICATIONS | 02/2026 |
4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations 4.2 Recommended Dose and Dosage Adjustment, 4.4 Administration | 02/2026 |
7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations; 7.1.1 Pregnant Women; 7.1.2 Breast-feeding; 7.1.3 Pediatrics; 7.1.4 Geriatrics | 02/2026 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................................... 2
TABLE OF CONTENTS ............................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................................... 4
- 1
INDICATIONS ........................................................................................................................... 4
- 1.1 Pediatrics .................................................................................................................................... 4
- 1.2 Geriatrics .................................................................................................................................... 4
- 2 CONTRAINDICATIONS .............................................................................................................. 4
- 3 SERIOUS WARNINGS AND PRECAUTIONS BOX .......................................................................... 4
- 4
DOSAGE AND ADMINISTRATION .............................................................................................. 5
- 4.1 Dosing Considerations ................................................................................................................ 5
- 4.2 Recommended Dose and Dosage Adjustment ........................................................................... 5
- 4.4 Administration ............................................................................................................................ 6
- 4.5 Missed Dose ............................................................................................................................... 6
- 5 OVERDOSAGE .......................................................................................................................... 6
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................................... 6
- 7
WARNINGS AND PRECAUTIONS ............................................................................................... 7
- 7.1 Special Populations ................................................................................................................... 14
- 7.1.1 Pregnant Women .......................................................................................................... 14
- 7.1.2 Breast-feeding ............................................................................................................... 15
- 7.1.3 Pediatrics....................................................................................................................... 15
- 7.1.4 Geriatrics ....................................................................................................................... 15
- 8
ADVERSE REACTIONS .............................................................................................................. 15
- 8.1 Adverse Reaction Overview ...................................................................................................... 15
- 8.2 Clinical Trial Adverse Reactions ................................................................................................ 16
8.5 Post-Market Adverse Reactions ............................................................................................... 18
- 9
DRUG INTERACTIONS .............................................................................................................. 19
- 9.2 Drug Interactions Overview ...................................................................................................... 19
- 9.4 Drug-Drug Interactions ............................................................................................................. 20
- 9.5 Drug-Food Interactions ............................................................................................................. 20
- 9.6 Drug-Herb Interactions ............................................................................................................. 20
- 9.7 Drug-Laboratory Test Interactions ........................................................................................... 20
- 10
CLINICAL PHARMACOLOGY ..................................................................................................... 21
- 10.1 Mechanism of Action ............................................................................................................. 21
- 10.2 Pharmacodynamics ................................................................................................................ 21
- 10.3 Pharmacokinetics ................................................................................................................... 22
- 11 STORAGE, STABILITY AND DISPOSAL ....................................................................................... 23
PART II: SCIENTIFIC INFORMATION ...................................................................................................... 24
- 13 PHARMACEUTICAL INFORMATION .......................................................................................... 24
- 14
CLINICAL TRIALS ...................................................................................................................... 25
- 14.1 Clinical Trial by Indication ....................................................................................................... 25
14.2 Comparative Bioavailability Studies ....................................................................................... 31
16 NON-CLINICAL TOXICOLOGY ........................................................................................................... 31
17 SUPPORTING PRODUCT MONOGRAPH ........................................................................................... 33
PATIENT MEDICATION INFORMATION ............................................................................................... 34
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
REDDY-PROGESTERONE (progesterone) is indicated for:
women with an intact uterus as an adjunct to postmenopausal estrogen replacement therapy to significantly reduce the risk of endometrial hyperplasia and carcinoma.
1.1 Pediatrics
REDDY-PROGESTERONE is not indicated for pediatric use.
1.2 Geriatrics
The evidence of safety and efficacy of progesterone is limited in women over 65 years of age; therefore, progesterone is not indicated in this population.
2 CONTRAINDICATIONS
REDDY-PROGESTERONE (progesterone) is contraindicated in patients with any of the following conditions:
- hypersensitivity to this drug, soya, peanut or to any ingredient in the formulation of the capsule. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- liver dysfunction or disease as long as liver function tests have failed to return to normal; see 7 WARNINGS AND PRECAUTIONS.
- personal history of known or suspected estrogen-dependent or progestin-dependent malignant neoplasia (e.g. breast cancer or endometrial cancer).
- endometrial hyperplasia.
- undiagnosed abnormal genital bleeding.
- known or suspected pregnancy.
- active or past history of arterial thromboembolic disease (e.g. stroke, myocardial infarction, coronary heart disease).
- active or past history of confirmed venous thromboembolism (such as deep venous thrombosis or pulmonary embolism) or active thrombophlebitis.
- partial or complete loss of vision due to ophthalmic vascular disease.
- Known thrombophilic disorders (e.g., protein C, protein S, or antithrombin deficiency).
- Porphyria.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
The Women’s Health Initiative (WHI) trial examined the health benefits and risks of combined estrogen plus progestin therapy (n=16,608) and estrogen-alone therapy (n=10,739) in postmenopausal women aged 50 to 79 years.
The estrogen plus progestin arm of the WHI trial indicated an increased risk of myocardial infarction (MI), stroke, invasive breast cancer, pulmonary embolism and deep vein thrombosis in postmenopausal women receiving treatment with combined conjugated equine estrogens (CEE, 0.625 mg/day) and medroxyprogesterone acetate (MPA, 2.5 mg/day) for 5.2 years compared to those receiving placebo.
The estrogen-alone arm of the WHI trial indicated an increased risk of stroke and deep vein thrombosis in hysterectomized women treated with CEE-alone (0.625 mg/day) for 6.8 years compared to those receiving placebo.
The Women’s Health Initiative Memory Study (WHIMS) estrogen plus progestin ancillary study of the WHI reported an increased risk of probable dementia in postmenopausal women 65 years of age or older.
Therefore, the following should be given serious consideration at the time of prescribing:
- Estrogens with or without progestins should not be prescribed for primary or secondary prevention of cardiovascular diseases or dementia.
- Estrogens with or without progestins should be prescribed at the lowest effective dose for the approved indication.
- Estrogens with or without progestins should be prescribed for the shortest period possible for the approved indication.
See 8 ADVERSE REACTIONS
Some of the information presented in the Warnings and Precautions section is provided in light of the fact that progestin medication is often prescribed concomitantly with an estrogen medication. Information in this section pertaining to combined estrogen-progestin therapy may therefore not apply to progestin-only therapy. Health Care Professional discretion is advised.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Pregnancy should be excluded before initiating HRT.
4.2 Recommended Dose and Dosage Adjustment
Hormone Replacement Therapy:
For initiation and continuation of hormone replacement therapy (estrogens and progesterone) in postmenopausal symptoms, the lowest effective dose for the shortest duration should be used (see also Section 7 WARNINGS AND PRECAUTIONS).
Serious Warnings and Precautions
In general, the dosage of REDDY-PROGESTERONE (progesterone) is 200 mg daily for the last 14 days of estrogen treatment per cycle (i.e. from day 8 to day 21 for a 28-day cycle, and from day 12 to day 25 for a 30-day cycle). Patients being treated with high dosages of estrogen (equivalent to 1.25 mg conjugated estrogens or higher) should be administered 300 mg daily for the last 12-14 days of estrogen treatment.
The dosage of REDDY-PROGESTERONE should be proportional to the dosage of estrogen. With adequate adjustment of the dosage of REDDY-PROGESTERONE, patients should experience either regular withdrawal uterine bleeding or cessation of bleeding (amenorrhea).
REDDY-PROGESTERONE is not indicated for paediatric use.
4.4 Administration
REDDY-PROGESTERONE is formulated for oral administration and must be swallowed whole. Capsules should not be chewed, crushed nor pierced.
The 200 mg daily dosage of REDDY-PROGESTERONE should be taken at bedtime. Patients receiving 300 mg REDDY-PROGESTERONE daily should take one capsule (100 mg) in the morning and two capsules (200 mg) at bedtime. The morning dose should be taken 2 hours after breakfast. Concomitant food ingestion significantly increases the bioavailability of micronised progesterone. See Section 9.5 DRUG-FOOD INTERACTIONS.
4.5 Missed Dose
If a patient is treated with 200 mg daily (total dose at bedtime) and she forgets to take this dose, she should take a dose of one capsule (100 mg) the following morning and continue taking the rest of the capsules as prescribed. If a patient is treated with 300 mg daily, and she forgets to take a morning or evening dose, she should not take the missed dose.
5 OVERDOSAGE
The toxicity of progesterone is very low. Symptoms that may occur are: nausea, vomiting, somnolence and dizziness.
Progestin (norethindrone acetate) overdosage has been characterized by depressed mood, tiredness, acne and hirsutism.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Table 1: Dosage Forms, Strengths, Composition
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
|---|---|---|
| Oral | Capsule, 100 mg progesterone | gelatin, glycerin, soya lecithin, peanut oil, titanium dioxide. |
REDDY-PROGESTERONE (micronized progesterone) 100 mg capsules to be taken orally; contain 100 mg micronized progesterone as the active ingredient.
REDDY-PROGESTERONE 100 mg capsule is a round, opaque, white, soft gelatin capsule.
The imprinting Opacode® S-1-277002 Black contains, ammonium hydroxide, black iron oxide, propylene glycol and shellac.
Packaging
REDDY-PROGESTERONE 100 mg progesterone capsules are available in unit dose blister packages, with 30 capsules per package and bottles of 100.
7 WARNINGS AND PRECAUTIONS
See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
REDDY-PROGESTERONE is NOT a contraceptive and must only be used in accordance with the indications in Section 1 INDICATIONS
Each Progesterone Soft Capsule 100 mg contains 1 mg soya lecithin and may cause hypersensitivity reactions (urticarial and anaphylactic shock in hypersensitive patients). As there is a possible relationship between allergy to soya and allergy to peanut, patients with peanut allergy should avoid using Progesterone Soft Capsules.
Progesterone Soft Capsules contain highly refined oil, for which the incidence of hypersensitivity is very rare in adults.
Carcinogenesis and Mutagenesis
Breast Cancer
Available epidemiological data indicate that the use of combined estrogen plus progestin by postmenopausal women is associated with an increased risk of invasive breast cancer.
In the estrogen plus progestin arm of the WHI trial (conjugated equine estrogens (CEE), 0.625 mg/day plus medroxyprogesterone acetate (MPA) 2.5 mg/day), among 10,000 women over a one-year period, there were:
- 8 more cases of invasive breast cancer (38 on combined HRT versus 30 on placebo).
The WHI study also reported that the invasive breast cancers diagnosed in the estrogen plus progestin group were similar in histology but were larger (mean [SD], 1.7 cm [1.1] vs. 1.5 cm [0.9], respectively; p=0.04) and were at a more advanced stage compared with those diagnosed in the placebo group. The percentage of women with abnormal mammograms (recommendations for short-interval follow-up, a suspicious abnormality, or highly suggestive of malignancy) was significantly higher in the estrogen plus progestin group versus the placebo group. This difference appeared at year one and persisted in each year thereafter.
In the estrogen-alone arm of the WHI trial (CEE at 0.625 mg/day), there was no statistically significant difference in the rate of invasive breast cancer in hysterectomized women treated with conjugated equine estrogens versus women treated with placebo.
It is recommended that estrogens with or without progestins not be given to women with existing breast cancer or those with a previous history of the disease. There is a need for caution in prescribing estrogens with or without progestins for women with known risk factors associated with the development of breast cancer, such as strong family history of breast cancer (first degree relative) or who present a breast condition with an increased risk (abnormal mammograms and/ or atypical hyperplasia at breast biopsy). Other known risk factors for the development of breast cancer such as nulliparity, obesity, early menarche, late age at first full term pregnancy and at menopause should also be evaluated.
It is recommended that women undergo mammography prior to the start of HRT treatment and at regular intervals during treatment, as deemed appropriate by the treating Health Care Professional and according to the perceived risks for each patient.
The overall benefits and possible risks of hormone replacement therapy should be fully considered and discussed with patients. It is important that the modest increased risk of being diagnosed with breast cancer after 4 years of treatment with combined estrogen plus progestin HRT (as reported in the results of the WHI trial) be discussed with the patient and weighed against its known benefits.
Instructions for regular self-examination of the breasts should be included in this counselling.
Endometrial hyperplasia & endometrial carcinoma
Estrogen-only HRT increases the risk of endometrial hyperplasia/carcinoma if taken by women with intact uteri. The role of progesterone, when combined with estrogen, is to prevent endometrial hyperplasia/carcinoma in women with intact uteri.
Ovarian cancer
Some recent epidemiologic studies have found that the use of hormone replacement therapy (estrogen-alone and estrogen plus progestin therapies), in particular for five or more years, has been associated with an increased risk of ovarian cancer.
Cardiovascular
The results of the Heart and Estrogen/progestin Replacement Studies (HERS and HERS II) and the Women’s Health Initiative (WHI) trial indicate that the use of estrogen plus progestin is associated with an increased risk of coronary heart disease (CHD) in postmenopausal women., The results of the WHI trial indicate that the use of estrogen-alone and estrogen plus progestin is associated with an increased risk of stroke in postmenopausal women.
WHI trial findings
In the combined estrogen plus progestin arm of the WHI trial, among 10,000 women over a one-year period, there were:
- 8 more cases of stroke (29 on combined HRT versus 21 on placebo)
- 7 more cases of CHD (37 on combined HRT versus 30 on placebo).
In the estrogen-alone arm of the WHI trial of women with prior hysterectomy, among 10,000 women over a one-year period, there were/was:
- 12 more cases of stroke (44 on estrogen-alone therapy versus 32 on placebo)
- no statistically significant difference in the rate of CHD.
HERS and HERS II findings
In the Heart and Estrogen/progestin Replacement Study (HERS) of postmenopausal women with documented heart disease (n=2763, average age 66.7 years), a randomized placebo- controlled clinical trial of secondary prevention of coronary heart disease (CHD), treatment with 0.625 mg/day oral conjugated equine estrogen (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) demonstrated no cardiovascular benefit. Specifically, during an average follow-up of 4.1 years, treatment with CEE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established coronary heart disease. There were more CHD events in the hormone-treated group than in the placebo group in year 1, but not during the subsequent years.
From the original HERS trial, 2321 women consented to participate in an open label extension of HERS known as HERS II. Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall. After 6.8 years, hormone therapy did not reduce the risk of cardiovascular events in women with CHD.
High Blood Pressure
Women using hormonal replacement therapy (HRT) sometimes experience increased blood pressure. Blood pressure should be monitored with HRT use. Elevation of blood pressure in previously normotensive or hypertensive patients should be investigated and HRT may have to be discontinued.
Driving and Operating Machinery
Transient and occasional somnolence or dizziness may occur in some patients 1-4 hours after ingestion of REDDY-PROGESTERONE, particularly if administered with food. Activities requiring concentration, good attention, good coordination or reflex action should be avoided when the above-mentioned neurological symptoms occur. In most cases, these problems can be avoided by taking the capsules at the recommended times. The 200 mg dosage should be taken at bedtime. The 300 mg dosage should be divided into two doses, 100 mg 2 hours after breakfast and 200 mg at bedtime.
Ear/Nose/Throat
Otosclerosis
Estrogens with or without progestins may cause an exacerbation of this condition, therefore caution should be taken.
Endocrine and Metabolism
Glucose and Lipid Metabolism
A worsening of glucose tolerance and lipid metabolism has been observed in a significant percentage of peri- and post-menopausal patients during treatment with HRT. Therefore, diabetic patients or those with a predisposition to diabetes should be observed closely to detect any alterations in carbohydrate or lipid metabolism, especially in triglyceride blood levels.
Women with familial hyperlipidemias need special surveillance. Lipid-lowering measures are recommended additionally before treatment is started.
Calcium and Phosphorus Metabolism
Because the prolonged use of estrogens, with or without progestins, influences the metabolism of calcium and phosphorus, estrogens should be used with caution in patients with metabolic and malignant bone diseases associated with hypercalcemia and in patients with renal insufficiency.
Genitourinary
Vaginal Bleeding
Abnormal vaginal bleeding, due to its prolongation, irregularity or heaviness, occurring during therapy should prompt diagnostic measures like hysteroscopy, endometrial biopsy or curettage to rule out the possibility of uterine malignancy and the treatment should be re-evaluated.
Uterine leiomyomata
Estrogens with or without progestins may increase the size of pre-existing uterine leiomyomata. Growth, pain or tenderness of uterine leiomyomata requires discontinuation of medication and appropriate investigation.
Endometriosis
Symptoms and physical findings associated with a previous diagnosis of endometriosis may reappear or become aggravated during the use of estrogens with or without progestins.
Hematologic
Venous Thromboembolism
Patients with known thrombophilic states have an increased risk of VTE and HRT may add to this risk. HRT is therefore contraindicated in these patients (see section 2 CONTRAINDICATIONS).
If a thrombophilic defect is identified which segregates with thrombosis in family members or if the defect is ‘severe’ (e.g., antithrombin, protein S, or protein C deficiencies or a combination of defects) HRT is contraindicated.
Available epidemiological data indicate that use of estrogen with or without progestin by postmenopausal women is associated with an increased risk of developing venous thromboembolism (VTE).
In the estrogen plus progestin arm of the WHI trial, among 10,000 women on combined HRT over a one-year period, there were 18 (34 on combined HRT versus 16 on placebo) more cases of venous thromboembolism, including 8 (16 on combined HRT versus 8 on placebo) more cases of pulmonary embolism.
In the estrogen-alone arm of the WHI trial, among 10,000 women on estrogen therapy over a one-year period, there were 7 (28 on estrogen therapy versus 21 on placebo) more cases of venous thromboembolism, although there was no statistically significant difference in the rate of pulmonary embolism.
Generally recognized risk factors for VTE include a personal history, a family history (the occurrence of VTE in a direct relative at a relatively early age may indicate genetic predisposition) and severe obesity (body mass index > 30 kg/m2). The risk of VTE also increases with age and smoking.
The risk of VTE may be temporarily increased with prolonged immobilization, major surgery or trauma. In women on HRT, attention should be given to prophylactic measures to prevent VTE following surgery. Also, patients with varicose veins should be closely supervised.
The Health Care Professional should be alert to the earliest manifestations of thrombotic disorders (thrombophlebitis, retinal thrombosis, cerebral embolism and pulmonary embolism). If these occur or are suspected, hormone therapy should be discontinued immediately, given the risks of long-term disability or fatality.
If feasible, estrogens with or without progestins should be discontinued at least 4 weeks before major surgery which may be associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
Hepatic/Biliary/Pancreatic
Liver disease
Particular caution is indicated in women with hepatic hemangiomas or hepatic adenomas as estrogens with or without progestins may cause an exacerbation of these conditions.
Gallbladder diseases
A 2- to 4-fold increase in the risk of gallbladder disease requiring surgery in women receiving postmenopausal estrogens has been reported. Particular caution is indicated in women with cholelithiasis, as estrogens with or without progestins may cause an exacerbation of this condition.
Jaundice
Caution is advised in patients with a history of liver and/or biliary disorders. If cholestatic jaundice or deteriorating liver function develops during treatment, the treatment should be discontinued and appropriate investigations carried out.
Liver Function Test
Liver function tests should be done periodically in subjects who are suspected of having hepatic disease. For information on endocrine and liver function tests, see section 9 DRUG INTERACTIONS/ Drug-Laboratory Interactions/Laboratory Tests.
Immune
Angioedema
Estrogens with or without progestins may induce or exacerbate symptoms of angioedema, in particular in women with hereditary angioedema.
Systemic lupus erythematosus
Particular caution is indicated in women with systemic lupus erythematosus, as estrogens with or without progestins may cause an exacerbation of this condition.
Monitoring and Laboratory Tests
Physical Examination
Before REDDY-PROGESTERONE (progesterone) is administered, the patient should have a complete physical examination including a blood pressure determination. Breasts and pelvic organs should be appropriately examined and a Papanicolaou smear should be performed. Endometrial biopsy should be done when indicated. Baseline tests should include mammography, measurements of blood glucose, calcium, triglycerides, cholesterol, and liver function tests.
The first follow-up examination should be done within 3-6 months after initiation of treatment to assess response to treatment. Examinations should include blood pressure, glucose tolerance, lipid metabolism, and liver function (see section 7 WARNINGS AND PRECAUTIONS – Endocrine and Metabolism; Cardiovascular; and Hepatic/Biliary/Pancreatic). Thereafter, examinations should be made at intervals at least once a year. Appropriate investigations should be arranged at regular intervals as determined by the Health Care Professional.
It is important that patients are encouraged to practice frequent self-examination of the breasts.
Neurologic
Cerebrovascular Insufficiency
Patients who develop visual disturbances, classical migraine, transient aphasia, paralysis, or loss of consciousness should discontinue medication.
Patients with a previous history of classical migraine and who develop a recurrence or worsening of migraine symptoms should be reevaluated.
Dementia
Available epidemiological data indicate that the use of combined estrogen plus progestin in women age 65 and over may increase the risk of developing probable dementia.
The Women’s Health Initiative Memory Study (WHIMS), a clinical substudy of the WHI, was designed to assess whether postmenopausal hormone replacement therapy (estrogen plus progestin or estrogen-alone) reduces the risk of dementia in women aged 65 and over and free of dementia at baseline.
In the estrogen plus progestin arm of the WHIMS (n=4532), women with an intact uterus were treated with daily 0.625 mg conjugated equine estrogens (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) or placebo for an average of 4.05 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 23 more cases of probable dementia (45 on combined HRT versus 22 on placebo).
In the estrogen-alone arm of the WHIMS (n=2947), women with prior hysterectomy were treated with daily 0.625 mg CEE or placebo for an average of 5.21 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 12 more cases of probable dementia (37 on estrogen-alone versus 25 on placebo), although this difference did not reach statistical significance.
When data from the estrogen plus progestin arm of the WHIMS and the estrogen-alone arm of the WHIMS were combined, as per the original WHIMS protocol, in 10,000 women over a one- year period, there were:
18 more cases of probable dementia (41 on estrogen plus progestin or estrogen-alone
versus 23 on placebo).
Epilepsy
Particular caution is indicated in women with epilepsy, as estrogens with or without progestins may cause an exacerbation of this condition.
Renal
Fluid Retention
Estrogens, with or without progestins, may cause fluid retention. Therefore, particular caution is indicated in cardiac or renal dysfunction or asthma. If, in any of the above-mentioned conditions, a worsening of the underlying disease is diagnosed or suspected during treatment, the benefits and risks of treatment should be reassessed based on the individual case.
7.1 Special Populations
7.1.1 Pregnant Women
Pregnancy should be excluded before initiating HRT. If pregnancy occurs during the use of progesterone, treatment should be withdrawn immediately.
If the patient is exposed to REDDY-PROGESTERONE (progesterone) capsules during the first 4 months of pregnancy or if she becomes pregnant while taking this drug she should be informed of the potential risks to the fetus.
A case of cleft palate was reported post-market following first trimester use (causality not established). Additionally rare cases of fetal death (causality not established) have been reported when progesterone was used for unapproved indications.
Cases of hepatocellular disease have been reported rarely in women treated with progesterone during the second and third trimester (see 8 ADVERSE REACTIONS).
7.1.2 Breast-feeding
Detectable amounts of progesterone have been identified in the milk of mothers receiving progesterone. REDDY-PROGESTERONE is not recommended during lactation.
7.1.3 Pediatrics
REDDY-PROGESTERONE is not indicated for pediatric use.
7.1.4 Geriatrics
The evidence of safety and efficacy of progesterone is limited in women over 65 years of age; therefore, REDDY-PROGESTERONE is not indicated in this population.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
See 7 WARNINGS AND PRECAUTIONS regarding potential induction of malignant neoplasms and adverse effects similar to those of oral contraceptives.
Adverse events that could be considered to be possibly associated with REDDY-PROGESTERONE (progesterone) therapy are: breakthrough bleeding, spotting, and menstrual irregularity.
Under the recommended conditions of use (200 mg HS), dizziness, somnolence, cramps or nausea have been reported occasionally. Fatigue, headache, vertigo, lightheadedness or migraine have been reported rarely.
Breast tenderness may occur with the use of REDDY-PROGESTERONE.
Other adverse events which are generally attributed to synthetic progestins and which may possibly occur during REDDY-PROGESTERONE treatment include: chloasma, pruritus, jaundice, rash, fluid retention, mental depression and thrombotic disorders.
The following adverse reactions have been reported with estrogen/progestin combinations in general:
Blood and Lymphatic System Disorders
Altered coagulation tests (see 9 DRUG INTERACTIONS/ Drug-Laboratory Interactions /Laboratory Tests).
Cardiac Disorders
Palpitations; increase in blood pressure (see 7 WARNINGS AND PRECAUTIONS); coronary thrombosis.
Endocrine Disorders
Increased blood sugar levels; decreased glucose tolerance.
Eye Disorders
Neuro-ocular lesions (e.g. retinal thrombosis, optic neuritis); visual disturbances; steepening of the corneal curvature; intolerance to contact lenses.
Gastrointestinal Disorders
Nausea; vomiting; abdominal discomfort (cramps, pressure, pain, bloating).
General Disorders and Administration Site Conditions
Fatigue; changes in appetite; changes in body weight; change in libido.
Hepatobiliary Disorders
Gallbladder disorder; asymptomatic impaired liver function; cholestatic jaundice.
Musculoskeletal and Connective Tissue Disorders
Musculoskeletal pain including leg pain not related to thromboembolic disease (usually transient, lasting 3-6 weeks) may occur.
Nervous System Disorders
Aggravation of migraine episodes; headaches; dizziness; neuritis.
Psychiatric Disorders
Mental depression; nervousness; irritability.
Renal and Urinary Disorders
Cystitis; dysuria; sodium retention; edema.
Reproductive System and Breast Disorders
Breakthrough bleeding; spotting; change in menstrual flow; dysmenorrhea ; vaginal itching/discharge; dyspareunia; endometrial hyperplasia; pre-menstrual-like syndrome; reactivation of endometriosis; changes in cervical erosion and amount of cervical secretion; breast swelling and tenderness.
Skin and Subcutaneous Tissue Disorders
Chloasma or melasma, which may persist when drug is discontinued; erythema multiforme; erythema nodosum; haemorrhagic eruption; loss of scalp hair; hirsutism and acne.
Vascular Disorders
Isolated cases of: thrombophlebitis; thromboembolic disorders.
If adverse symptoms persist, the prescription of HRT should be re-considered.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 2 lists adverse reactions experienced in a double-blind, randomized, parallel-group study that compared the efficacy and safety of progesterone 200 mg and 300 mg with placebo for a duration of treatment of 10 days. Two patients withdrew from the study prior to receiving study drug. The majority of adverse reactions experienced are those resulting from the pharmacological action of progesterone as well as from the onset of withdrawal bleeding. These events include cramping, nausea, abdominal pain and/or bloating and tender or swollen breasts.
Table 2: Adverse Reactions Reported in a 60 Patient Double-Blind, Randomized, Parallel-Group Study [Percentage (%) of Patients Reporting]
Progesterone 200 mg N=19 | Progesterone 300 mg N=19 | Placebo N=21 | |
|---|---|---|---|
| Cramps | 58% | 35% | 29% |
| Nausea | 5% | 15% | 10% |
| Breast Tenderness | 5% | 10% | 19% |
| Abdominal Discomfort | 5% | 10% | 14% |
| Dizziness | 11% | 15% | 14% |
| Tired/Lethargy | 21% | 20% | 14% |
Dupont et al conducted a single-blind, randomized, controlled study that compared percutaneous estradiol and oral conjugated estrogens as replacement therapy (with or without progesterone) in sixty-three healthy postmenopausal women for 24 weeks. In this study, serum aldosterone concentrations were slightly elevated in subjects receiving progesterone independent of the form of estrogen therapy administered. The increase in aldosterone was not associated with any clinical symptoms or side effects. There was no significant change in diastolic and systolic blood pressure.
Table 3 lists adverse experiences which were reported in ≥2% of patients (regardless of relationship to treatment) who received cyclic progesterone, 200 mg daily (12 days per calendar month cycle) with daily 0.625 mg conjugated estrogen, in a multicenter, randomized, double-blind, placebo-controlled clinical trial (Postmenopausal Estrogen and Progestin Interventions (PEPI) Trial) in 875 postmenopausal women. Table 3 also lists adverse experiences reported in the conjugated estrogen-alone group and placebo group of the PEPI trial.
Table 3: Adverse Experiences (≥2%) Reported in an 875 Patient Placebo-Controlled Trial in Postmenopausal Women over a 3-Year Period [Percentage (%) of Patients Reporting]
Progesterone Capsules 200 mg with Conjugated Estrogens 0.625 mg | Conjugated Estrogens 0.625 mg (only) | Placebo | ||||||
|---|---|---|---|---|---|---|---|---|
| (N=178) | (N=175) | (N=174) | ||||||
| Headache | 31 | 30 | 27 | |||||
| Breast Tenderness | 27 | 16 | 6 | |||||
| Joint Pain | 20 | 22 | 29 | |||||
| Depression | 19 | 18 | 12 | |||||
| Dizziness | 15 | 5 | 9 | |||||
| Abdominal Bloating | 12 | 10 | 5 | |||||
| Hot Flashes | 11 | 14 | 35 | |||||
| Urinary Problems | 11 | 10 | 9 | |||||
| Abdominal Pain | 10 | 13 | 10 | |||||
| Vaginal Discharge | 10 | 10 | 3 | |||||
| Nausea / Vomiting | 8 | 6 | 7 | |||||
| Worry | 8 | 5 | 4 | |||||
| Chest Pain | 7 | 4 | 5 | |||||
| Diarrhea | 7 | 7 | 4 | |||||
| Night Sweats | 7 | 5 | 17 | |||||
| Breast Pain | 6 | 6 | 2 | |||||
| Swelling of Hands and Feet | 6 | 9 | 9 | |||||
| Vaginal Dryness | 6 | 8 | 10 | |||||
| Constipation | 3 | 3 | 2 | |||||
8.5 Post-Market Adverse Reactions
During the marketing of progesterone internationally, cases of hepatocellular liver disease have been reported rarely. Most of these occurred in women treated outside of the approved indications, i. e., during the second and third trimester of pregnancy when premature labour was threatened.
Additional post-market adverse experiences without well established cause-relationship have been observed in women taking progesterone:
- Blood and lymphatic disorders: Anaemia
- Cardiac disorders: Tachycardia
- Ear and labyrinth disorders: Tinnitus
- Eye disorders: Eye irritation
- Gastrointestinal disorders: Abdominal distension, taste disturbances
- General disorders and administration site conditions: Malaise, asthenia, chest discomforts, pyrexia
- Immune system disorder: Anaphylaxis and anaphylactoid reactions
- Infection and infestations: Urinary tract infections, vaginitis
- Musculoskeletal and connective tissue disorders: Arthralgia, back pain, limb discomfort, muscle spasms, myalgia
- Nervous system disorders: Speech disorder, amnesia, paraesthesia, syncope
- Psychiatric disorders: Insomnia, agitation, anxiety, apathy, disorientation, mood swings
- Reproductive system and breast disorders: Vaginal haemorrhage, amenorrhoea, metrorrhagia, vulvovaginal discomfort, mastodynia
- Respiratory, thoracic and mediastinal disorders: Dyspnoea
- Skin and subcutaneous tissue disorders: Hyperhidrosis, urticaria
- Vascular disorders: Haemorrhage, hypotension
If adverse symptoms persist, the prescription of HRT should be re-considered.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Progestogens may affect the treatment balance of diabetes. The diabetes medicine of patients being treated simultaneously with progestogens may need to be adjusted.
Progesterone may prevent the metabolism of ciclosporin, which increases the concentration ciclosporin concentrations and a risk of toxicity.
Medicines known to induce the hepatic enzyme CYP450-3A4 may increase the metabolism and elimination of progesterone, possibly resulting in a decrease in therapeutic effects and/or changes in uterine bleeding profile. These medicines may include:
- Some antibiotics: rifampicin, rifabutin
- Epilepsy medicines (not valproic acid): phenytoin, phenobarbital, carbamazepine, and topiramate
- Nonnucleoside reverse transcriptase inhibitors: nevirapine, efavirenz
- Sedatives: barbiturates, meprobamate
- Bosentan
Medicines known to inhibit the metabolism of progesterone can lead to an increase in the bioavailability of progesterone, possibly resulting in side effects. These medicines may include:
- Antifungal medicines: fluconazole, itraconazole, ketoconazole, voriconazole
- Antiretroviral medicines: ritonavir, nelfinavir
- Immunosuppressants: tacrolimus
Clinical pharmacokinetic studies have not demonstrated any consistent effect of antibiotics (other than those that are hepatic enzyme inducers) on plasma concentrations of synthetic steroids.
9.4 Drug-Drug Interactions
No drug-drug interaction studies have been conducted with progesterone.
9.5 Drug-Food Interactions
Concomitant food ingestion increased the AUC and Cmax values of progesterone, with no effect on Tmax relative to a fasting state when administered to postmenopausal women at a dose of 200 mg, for information see 10 CLINICAL PHARMACOLOGY/10.1 Mechanism of Action/10.3 Pharmacokinetics
9.6 Drug-Herb Interactions
It was found that some herbal products (e.g. St-John’s wort, Hypericum perforatum), which are available as OTC products, might affect metabolism, and therefore, efficacy and safety of estrogen/progestin products.
Health Care Professionals and other health care providers should be aware of other non- prescription products concomitantly used by the patient, including herbal and natural products, obtained from the widely spread Health Stores.
- Drug-Laboratory Test Interactions Laboratory Tests
The following laboratory results may be altered by the use of progesterone: levels of gonadotropin, plasma progesterone, and urinary pregnanediol.
The results of certain endocrine and liver function tests may be affected by progestin- containing products:
- impaired glucose tolerance;
- reduced serum folate concentration;
- change in plasma lipoprotein levels.
The results of the above laboratory tests should not be considered reliable unless therapy has been discontinued for two to four weeks. The pathologist should be informed that the patient is receiving HRT therapy when relevant specimens are submitted.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
REDDY-PROGESTERONE (progesterone) is an oral dosage form of the naturally occurring steroid; it is chemically identical to progesterone of ovarian origin.
Progestins are used in combination with estrogens to prevent estrogen-induced endometrial hyperplasia and reduce the risk of endometrial carcinoma to that of untreated women.
10.2 Pharmacodynamics
REDDY-PROGESTERONE is intended for use in women with an intact uterus as an adjunct to estrogen replacement therapy. Progesterone exerts significant anti-proliferative effects on the estrogenized endometrium and maintains sufficient control of endometrial mitotic activity through suppression of nuclear estradiol receptors, significant reduction in epithelial and stromal DNA synthesis and induction of 17ß-estradiol dehydrogenase and isocitric dehydrogenase activity.
REDDY-PROGESTERONE has the same effects as natural endogenous progesterone. It reduces mitotic activity in the endometrial glandular cells; the endometrium is transformed like in the physiological cycle sequence. Secession may lead to withdrawal bleeding. REDDY-PROGESTERONE significantly reduces the oestrogen-induced risk of endometrial hyperplasia in non- hysterectomised women. This is of particular significance in cases of prolonged oestrogen therapy during the menopause.
REDDY-PROGESTERONE acts as slight nitrogen catabolic but has neutral or very little effect on serum lipids, calcium metabolism, blood pH, and on hormones such as prolactin, oestradiol, oestrone. The mineralocorticoid effect of progesterone metabolites is itself largely antagonized by the antimineralocorticoid effect of progesterone.
REDDY-PROGESTERONE has no oestrous or androgenic effects.
REDDY-PROGESTERONE acts mainly antioestrogenically at low doses (200 mg / day).
REDDY-PROGESTERONE administered per os is a physiologic inhibitor of aldosterone and thus increases the sodium excretion rate. A 200 mg dose of micronized progesterone is equivalent to a dose of 25 to 50 mg of spironolactone as an aldosterone inhibitor.
Progesterone has no significant effect on carbohydrate metabolism, even when administered to non-insulin dependent diabetics. Progesterone does not negate the beneficial oral or transdermal estrogen-induced effect on lipoprotein profiles. In general, administration of progesterone (with or without estrogen) does not lead to significant changes in systolic and diastolic blood pressure or heart rate in normotensive women. Administration of progesterone does not lead to any significant change in renin substrate, even when administered to diabetic patients. Administration of progesterone in combination with percutaneous estradiol produces a decrease in blood platelet aggregation in perimenopausal women. In combination with oral conjugated estrogens, progesterone does not negatively affect the balance between the vasoactive prostanoids PGI2 and TxA2.
- Pharmacokinetics Absorption and Distribution
Pharmacokinetic studies indicate that plasma progesterone levels within the luteal range are achieved with peak levels (mean 77.3 nmol/L) at 2-4 hours following oral administration to postmenopausal women of progesterone 200 mg.
Table 4: Mean Pharmacokinetic parameters in postmenopausal women after five daily doses of progesterone capsules.
| Mean (n=15) Day 5 Progesterone Cmax and AUC Values after Administration of Progesterone 200 and 300 mg Once-Daily | ||
| Progesterone Dose (mg/day) | ||
| 200 | 300 | |
| Cmax (nmol/L) | 121.2 | 192.7 |
| AUC 0-10 (nmol∙hr/L) | 321.8 | 558.7 |
The plasma concentration of progesterone then declines slowly but remains within the range found in the mid-luteal phase for approximately 9 to 12 hours after administration. Plasma progesterone levels remain above baseline 84 hours after administration of the final dosage. Ingestion of food following administration of progesterone significantly increases AUC and Cmax values, with no effect on Tmax. Bioavailability (defined as area under the curve, AUC) is linearly related to the dose.
Progesterone concentrations measured in the endometrium after 8 days of treatment with progesterone either 200 mg/day or 300 mg/day are comparable to physiologic levels during the luteal phase even 12 hours after administration. This fact demonstrates the strong retention of this hormone in target tissue, which is responsible for its biological action during 24 hours. Similarly, significant increases in progesterone concentrations occur in breast tissue.
Intestinal absorption is rapid. Micronization of progesterone improves its absorption by the digestive tract by increasing the surface area in contact between the steroid and the mucous membrane.
Metabolism and Excretion
Following administration of progesterone 300 mg, the major inactive metabolite (pregnanediol-3 α glucuronide) and the 2 major active metabolites (17-hydroxyprogesterone, 20 α dihydroprogesterone) show similar plasma profiles to progesterone. Twenty-four hours following oral administration of 200 mg of progesterone to postmenopausal women, 22.8 mg of pregnanediol glucuronide are eliminated in urine. The second major excretion pathway is via the bile and the feces.
Since progesterone is metabolized primarily by the liver and is excreted mainly in the urine, patients with illness related to the liver and/or kidneys should be monitored closely.
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature 15°-30°C. Protect from light. Keep in a safe place out of the reach of children and pets.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
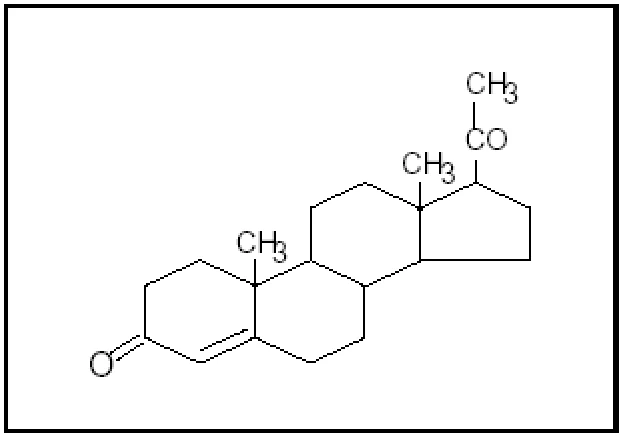
Proper name: Progesterone, U.S.P. micronized Chemical name: Pregn-4-ene-3,20-dione Molecular formula: C21H30O2
Molecular mass: 314.47 (g/mol). Structural formula:
Physicochemical properties:
Physical form: White or creamy white, odorless, crystalline powder.
Solubility: Practically insoluble in water; soluble in alcohol and in dioxane; sparingly soluble in vegetable oils.
Melting range: 126°C - 131°C.
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
Adjunct to postmenopausal estrogen replacement therapy to significantly reduce the risk of endometrial hyperplasia and carcinoma in women with intact uterus
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| Moyer 1993 | Long-term, open, non- controlled, single-centre observational expanded clinical case report study. (Biopsy done in 1987 or 1988 after a minimum of 5 years of unchanged treatment | Progesterone capsule Oral (Progesterone)
Minimum 5 years follow up | 236 | Not specified. All these nonhysterecto mized women had amenorrhea for 12 months or more, a plasma E2 level <147 pmol/dL and plasma FSH and LH > 20 IU/L. | Female |
| Shangold 1991 | Phase 3 Single center, prospective, randomized, double blind, placebo controlled study (3 parallel groups). | Progesterone capsule Oral (Progesterone) 200 mg/day 300 mg/day Placebo Duration: 10 days (final interview 2 to 4 weeks after completing medication | 60 | 18 to 52 years old | Female |
| Dupont 1991 | A single-blind, randomized, controlled study | Oral (CEE, 0.625 mg) tablet or percutaneous gel (estrogel 2.5 mg) from day 1 to day 25
Duration: 6 months | 63 | 50 years (37- 59) | Female |
|---|---|---|---|---|---|
PEPI ClinicalT rials.gov ID NCT0 0000466 Howard for The Writing Group for the PEPI Trial 1996; Lindenfel d 2002 | Phase 3, 3 year multicenter interventional, randomized, double- masked, placebo- controlled clinical trial |
Duration: 3 years * Progesterone capsule Oral | 596 | Postmenopaus al women, ages 45 to 64 | Female |
| Kim 1996 | Controlled, open, parallel group, pilot pharmacodyna mic study | Group 1: 300 mg oral micronized progesterone daily Group 2: 300 mg oral micronized progesterone twice daily from study days 1 through 14 after estradiol priming treatment for 30 days Duration: 14 days | 12 | Group 1: 55.3 (SEM: 2.2). Group 2: 59.5 (SEM: 1.9) | Female |
A long-term study evaluated the efficacy and safety of progesterone (micronized progesterone) 200 mg and 300 mg to prevent endometrial hyperplasia in postmenopausal women receiving long term Hormone Replacement Therapy (HRT) (Moyer 1993). The study also aimed to identify those characteristics of endometrial morphology that are essential for long term safety in postmenopausal women who are receiving different combinations of estradiol and progesterone over a period of five or more years. Two hundred thirty-six (236) women having natural symptomatic menopause and seeking hormone replacement therapy were initiated into the study.
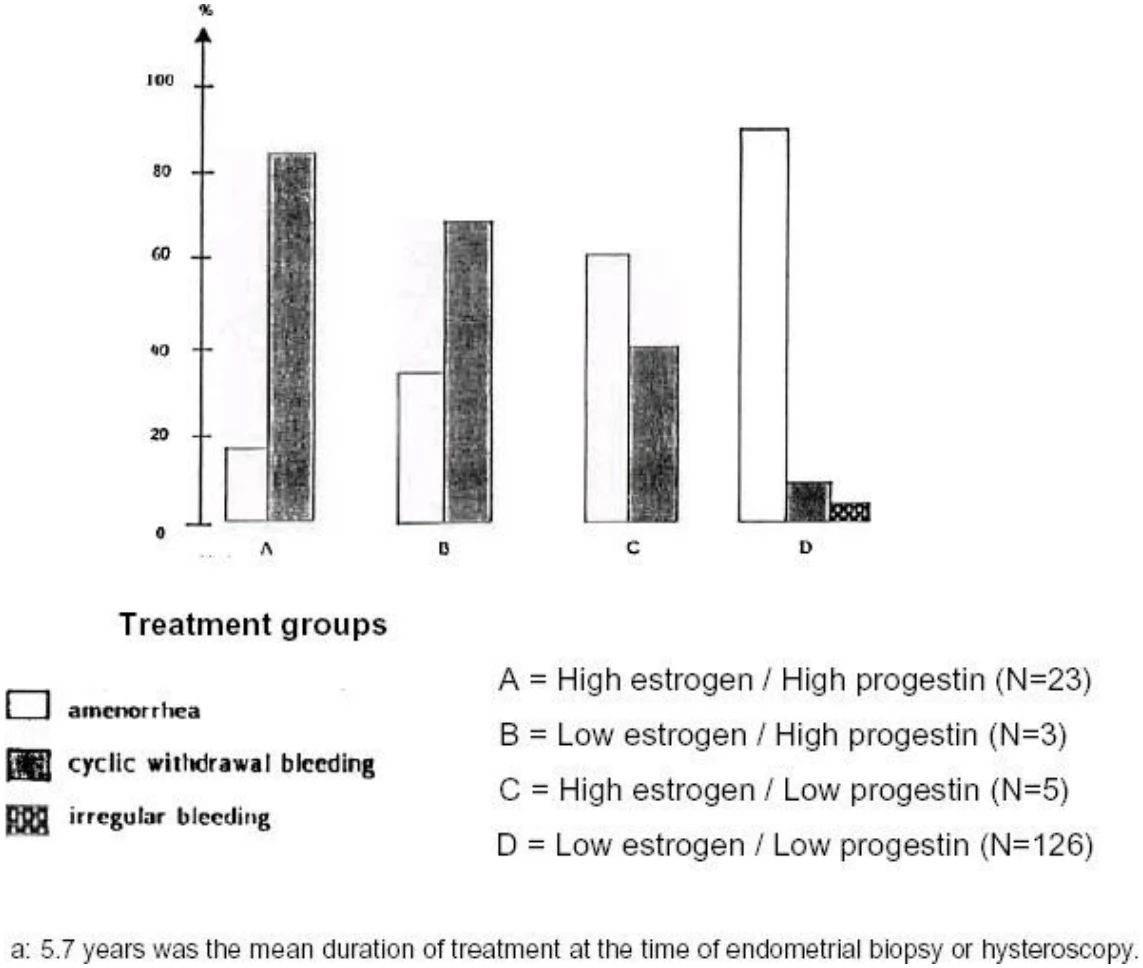
The women were treated with an initial low dose of 1.5 mg percutaneous estradiol, for 21 days out of 28, and 200 mg oral micronized progesterone, given for the last 14 days of estrogen treatment. Within the first 6 months of treatment, the initial progesterone dose was eventually increased to 300 mg in patients willing to have regular withdrawal bleeding and who did not have it with 200 mg per day. The monthly duration of estradiol treatment was prolonged to 25 days out of 28 in the case of recurrence of clinical symptoms during the treatment free week and the monthly duration of oral micronized progesterone treatment was shortened to 10 or 12 days in the case of early uterine bleeding appearing before the end of the course of each cycle of treatment. The 200 mg progesterone dose was given at bedtime. The 300 mg dose was divided into 100 mg taken in the morning and 200 mg at bedtime. The treatment groups were as follow: 126 women received 1.5 mg estradiol plus 200 mg micronized progesterone (Treatment Group A), 3 women received 1.5 mg estradiol plus 300 mg micronized progesterone (Treatment Group B), 5 women received 3 mg estradiol plus 200 mg micronized progesterone (Treatment Group C) and 23 women received 3 mg estradiol plus 300 mg micronized progesterone (Treatment Group D).
Of the 236 women initiated into this study, 79 dropped out during the first 5 years of treatment. The primary reasons for not continuing treatment were the lack of recurrence of initial clinical symptoms after several years of HRT or fear of potential side effects of HRT. These patients were not included in statistical analysis. In the 4 women who developed irregular bleeding while under treatment, a dilation and curettage was performed. The tissue morphology showed benign endometrial polyps in 3 cases and a fourth woman was diagnosed as having a submucosal leiomyoma. None of these four women showed either endometrial hyperplasia or carcinoma. An increased incidence of amenorrhea was seen with the treatment groups (E=estrogen, P=progestin): high E/high P < low E/high P < high E/low P < low E/low P (see also Figure 1).
An inverse relationship was seen for the incidence of withdrawal bleeding. Incidences of irregular bleeding were reported in the low estrogen/low progestin group. The combinations of percutaneous estradiol and progesterone used in this study were sufficient to protect the endometrium from hyperplasia and adenocarcinoma. Administration of oral micronized progesterone (200 mg/day) was sufficient to significantly reduce mitotic activity in the endometrial glandular cells with a maximal reduction noted after a mean of 11 days of progesterone exposure. The progesterone antiproliferative effects (decrease in epithelial mitotic activity) may be separated from other secretory changes (stromal pseudostratification and glandular secretion).
Figure 1: Bleeding patterns during the last 12 months of the 5.7 yearsa study according to different estradiol/progesterone treatments.
A double-blind, randomized, parallel-group study compared the efficacy and safety of progesterone 200 mg and 300 mg with placebo, in the initiation of withdrawal bleeding in patients with secondary amenorrhea (Shangold 1991). The duration of treatment was 10 days, and the efficacy on withdrawal bleeding was determined over a 16-day period (10 treatment days plus 1 week following the final dose). Efficacy analysis was based on sixty women receiving either progesterone 200 mg (100 mg x 2 capsules + 1 placebo capsule) (19 women), 300 mg (100 mg x 3 capsules) (20 women) or placebo (3 capsules) (21 women), once daily at bedtime. Patients were assessed for withdrawal bleeding from the beginning of treatment up to and including one week following the final dose. Efficacy of the progesterone treatment was determined by comparing each of the progesterone groups to the placebo group with respect to the initiation of withdrawal bleeding.
Table 5 summarizes withdrawal bleeding results following treatment in all 3 groups. Ninety percent (90%) (18/20) of the patients in the progesterone 300 mg group experienced withdrawal bleeding as compared to 53% (10/19) in the progesterone 200 mg group and 24% (5/21) in the placebo group. The proportion of patients experiencing withdrawal bleeding in the progesterone 300 mg group was significantly greater than in the placebo group (one- tailed p<0.001); whereas the progesterone 200 mg group was not significantly different from the placebo group (one-tailed p>0.05). There was a significant difference between the two treatment groups (two-tailed p=0.0253). Approximately twice as many patients in the progesterone 300 mg group had withdrawal bleeding as compared to the 200 mg group (90% vs. 53%).
Table 5: Withdrawal Bleeding with Progesterone and Placebo.
Progesterone 200 mg N=19 | Progesterone 300mg N=20 | Placebo N=21 | |
| Patients having withdrawal bleeding | 53% | 90% | 24% |
| Average number of days until withdrawal bleeding | 8.7 | 10.7 | 10.4 |
A single-blind, randomized, controlled study compared oral and percutaneous routes of administration of estrogen, given either with or without progesterone, as HRT for menopause. Criteria of effectiveness included transformation of the endometrium and endocrine profiles.
Sixty-three healthy postmenopausal women entered the study. Percutaneous estradiol (2.5 mg) or oral conjugated estrogens (0.625 mg) was administered daily to hysterectomized (31 women) and non-hysterectomized (32 women) women from day 1 to day 25 of a 28-day cycle. Non-hysterectomized women also received 200 mg progesterone on day 12 to day 25 of the 28-day cycle. In all cases, no treatment was administered during days 26 to 28. The duration of treatment was 6 months. Blood samples were obtained from each participant prior to treatment and throughout the replacement therapy. Serum LH, FSH and progesterone were determined. The 32 non-hysterectomized women had endometrial biopsies obtained by curettage before and after 24 weeks of replacement therapy. Morphological evaluation was assessed by light microscopy.
No patients dropped out during this study. Addition of progesterone increased the inhibitory effect of the estrogen preparations on both LH and FSH. Serum progesterone levels fluctuated between 6 and 10 nmoL/L for the day 12 to day 25 period of each cycle, which is characteristic of levels seen during late luteal phases. Serum LH concentrations were lowered to 67, 79, 62 and 67% of their pretreatment concentrations following transdermal estradiol + progesterone, transdermal estradiol alone, oral conjugated estrogens + progesterone and oral conjugated estrogens alone, respectively, while FSH serum levels were respectively decreased to 60, 80, 46 and 57% of pretreatment values. Mitotic activity remained low in all cases after three or more days of progesterone treatment, and no patients showed cystic or glandular hyperplasia. The anti-proliferative endometrial control seen in patients receiving 200 mg progesterone in addition to either estrogen preparation appeared sufficient in all patients. Most of the patients
(47%) remained amenorrheic and 34% had regular withdrawal bleeding.
progesterone administration did not influence the activity of 17β-hydroxysteroid dehydrogenase as the conversion of estrone to estradiol was similar in both groups of women receiving oral conjugated estrogens with or without progesterone.
Lindenfeld et al. evaluated the bleeding patterns with common regimens of HRT using two different progestogens in the Postmenopausal Estrogen and Progestin Interventions Trial (PEPI 1996). A total of 875 women in the PEPI trial took either placebo, conjugated equine estrogen 0.625 mg, conjugated equine estrogen 0.625 mg plus medroxyprogesterone acetate (MPA) 2.5 mg in a continuous fashion, or conjugated equine estrogen 0.625 mg daily plus either cyclical MPA 10 mg or cyclical progesterone 200 mg/day for 12 days per month. For 596 patients with a uterus, bleeding days, amounts, and episodes were recoded for 3 years (Lindenfeld 2002).
Conjugated equine estrogens plus progesterone cyclical was associated with fewer excess episodes of bleeding than conjugated equine estrogen plus MPA continuous in the first 6 months. Quantities of bleeding for conjugated equine estrogen plus progesterone cyclical were less than for conjugated equine estrogen plus MPA cyclical through 30 months and for the number of bleeding days through study end.
As part of the Postmenopausal Estrogen/Progestin Interventions (PEPI) Trial, a study by Judd Howard L. et al. was conducted and aimed to examine the effects of hormone replacement therapy on the endometrial histology of postmenopausal women. The research was conducted on 596 women aged 45 through 64 years without contraindication to hormone therapy.
Histology of endometrium were collected at baseline, annual or unscheduled visits by biopsy, curettage or hysterectomy. The results showed that women assigned to estrogen alone had a higher likelihood of developing various types of endometrial hyperplasia compared to those given placebo. However, women administered one of the three estrogen plus progestin regimens had hyperplasia rates that were not significantly different compared to those given placebo. In conclusion, the study found that daily administration of conjugated equine estrogens (CEE) at a dosage of 0.625 mg increased the risk of endometrial hyperplasia.
However, combining CEE with cyclic or continuous medroxyprogesterone acetate (MPA) or cyclic micronized progesterone (MP) helped protect the endometrium from hyperplastic changes associated with estrogen-only therapy.
Kim et al. study design was to explore the differential threshold of the biologic endpoints of antiproliferation and secretory conversion of the endometrium by different regimes of oral progesterone (Kim 1996). Patients were given 300 mg progesterone daily (8:00 am) or twice (8:00 am and 4:00 pm) daily from study days 1 through 14 after estrogen priming for 30 days.
The pharmacodynamic effect was examined by endometrial biopsies with regards to histology, glycogen content of glands, ribosomal RNA, and nuclear estrogen receptors in glands, surface epithelium, and stroma. Dose-dependent increases in glandular glycogen, decrease in ribosomal RNA, and decrease in nuclear estrogen receptors were demonstrated. The authors concluded that sustained low concentrations of progesterone probably are sufficient to inhibit endometrial overgrowth and hyperplasia. Ultimately, oral progesterone can induce antiproliferative changes in the human endometrium at doses lower than those required for transformation of the endometrium to a full secretory state.
14.2 Comparative Bioavailability Studies
A blinded, balanced, randomized, two-treatment, four-period, two-sequence, single dose, full replicate, oral bioequivalence study of REDDY-PROGESTERONE (Dr. Reddy’s Laboratories, Inc.) and PROMETRIUM® (Merck Canada Inc.,) was conducted in healthy, adult, human males and post-menopausal female subjects under fasting conditions. Comparative bioavailability data from 58 subjects that were included in the statistical analysis are presented in the following table:
Progesterone [Baseline Corrected Data] (1 x 100 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (pg⋅h/mL) | 5750.7 13986.4 (274.2) | 6117.9 18845.9 (286.0) | 94.0 | 83.1-106.3 |
AUCI (pg⋅h/mL) | 6240.0 15043.8 (270.4) | 7052.6 21618.4 (285.2) | 88.5 | 80.7-97.0 |
CMAX (pg/mL) | 1521.6 3619.9 (259.0) | 1741.0 5834.4 (275.8) | 87.4 | 76.7-99.5 |
TMAX3 (h) | 1.67 (0.67-10.00) | 2.00 (0.67-10.00) | ||
| T½4 (h) | 7.15 (65.7) | 6.82 (62.2) | ||
1 REDDY-PROGESTERONE (progesterone) capsules, 100 mg (Dr. Reddy’s Laboratories, Inc.)
2 PROMETRIUM® (progesterone) capsules, 100 mg (Merck Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 NON-CLINICAL TOXICOLOGY
The toxicology of micronized progesterone has been studied in rats, rabbits and dogs. The biological effects of micronized progesterone have been demonstrated by increased uterine weight, endometrium development and deciduoma formation in rats and rabbits pretreated with estradiol.
General toxicology
Subacute oral toxicity in rats has been studied with daily doses of 40, 100 and 250 mg/kg for 4 weeks as well as daily doses of 5, 15, 45 and 135 mg/kg for 12 weeks. In both subacute studies no mortalities occurred at any treatment level and no toxic or untoward effects were observed at 5, 15, 40 and 45 mg/kg. Signs of sedation, relaxation and coma were seen at higher dose levels (135 and 250 mg/kg) and salivation was seen with a dose of 100 mg/kg. Dose related weight gain was observed in females at the 100 and 250 mg/kg/day dosage. Hematological studies revealed modest decreases in circulating proteins after 3 months, with inconsistent effects on white blood cell counts. No other significant treatment related effects were observed in clinical signs or histopathology in either study.
In dogs, the subacute oral toxicity of micronized progesterone was studied at daily doses of 50, 125 and 325 mg/kg for 12 weeks. No mortalities were observed at any dose level. Treatment related effects included irritability and sedation in animals receiving 325 mg/kg and serum biochemical alterations at all levels of treatment. Changes in serum cholesterol, lipoproteins, total lipids and electrolyte balance were observed in the treated animals. Target tissue effects of micronized progesterone in treated animals included histopathological findings such as adenosic disease of the breast, ovarian cysts and cystic dysplasia of the endometrium.
Treatment related histological changes were not observed in other tissues.
Genotoxicity
Progesterone was negative in vitro for point mutations in the Ames test, in E. coli bacteria, and in the mouse lymphoma forward mutation assay.
Progesterone did not cause mitotic disturbances or chromosome aberrations in Chinese hamster fibroblast cells in culture and did not cause an increase in unscheduled DNA synthesis in hepatocytes from male Fischer 344 rats in culture.
Progesterone was negative in assays for chromosome damage using human female leukocytes, or by the sister chromatid exchange (SCE) assay in human female peripheral blood lymphocytes (HPBL) or in human fibroblast cells.
Chromosome changes were observed in Chinese hamsters receiving SC injections of progesterone for up to four weeks, and in the testes of male mongrel dogs injected IM every other day for six weeks. Since the doses in these studies would have produced blood levels of progesterone in the endogenous range, the toxicological significance of the results is unclear.
Carcinogenicity
Subcutaneous implantation of progesterone pellets in mice resulted in increases in ovarian granulosa cell tumors and endometrial sarcomas, metaplasia in the endocervical mucosa, squamous cell carcinomas of the cervicovaginal region and hyperplastic nodules of the mammary gland. The findings of tumors in the reproductive tissues of rodents are consistent with that observed with other progestational compounds.
Female beagle dogs, treated with progesterone administered by SC or IM injection for up to four years, developed endometrial and mammary hyperplasia (SC injection) and mammary gland nodules, including two carcinomas (IM injection). The Food and Drug Administration of the United States has concluded that the female Beagle is not an appropriate model for mammary carcinogenicity testing of progestins.
Reproductive and Developmental Toxicology
Administration of progesterone by SC injection to pregnant mice resulted in a decrease in sexual behavior in male offspring with no changes to internal or external genitalia, and an increase in aggressive behavior in female offspring. No abnormalities of internal or external genitalia were observed in the offspring of rats treated with progesterone by SC injection.
No adverse effect on egg development was observed following oral (gavage) administration of progesterone to rabbits three days before or after mating. SC dosing of pregnant rabbits also had no adverse effect on egg development, while SC dosing two days prior to mating induced complete degeneration of eggs. Single SC injection to rabbits before mating did not impair fertility but led to embryonic death by day 4 of gestation.
Administration of progesterone by IM injection to pregnant rhesus monkeys did not cause any adverse effects on pregnancy or on the incidence of anomalies in the offspring.
17 SUPPORTING PRODUCT MONOGRAPH
- 1. PrPROMETRIUM Capsules, 100 mg, submission control 295264, Product Monograph, Organon Canada Inc. (JUL 17, 2025)