


Product Monograph - Renvela (Sanofi-Aventis Canada, 800 mg)
Recent Major Label Changes
| 4 Dosage and Administration, 4.1 Dosing Considerations | 2026-04 |
|---|---|
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 2026-04 |
| 7 Warnings and Precautions, 7.1.3 Pediatrics | 2026-04 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics (6 - <18 years of age) ................................................................................ 4
1.2. Geriatrics (≥ 65 years of age) .................................................................................... 4
- 2. Contraindications ............................................................................................................ 4
- 3. Serious Warnings and Precautions Box ............................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 4
4.1. Dosing Considerations .............................................................................................. 4
4.2. Recommended Dose and Dosage Adjustment ......................................................... 5
4.4. Administration .......................................................................................................... 7
4.5. Missed Dose ............................................................................................................. 7
- 5. Overdose ......................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 8
- 7.
Warnings and Precautions ............................................................................................... 8
General ................................................................................................................................. 8
Gastrointestinal .................................................................................................................... 9
Monitoring and Laboratory Tests ......................................................................................... 9
7.1. Special Populations .................................................................................................. 9
7.1.1. Pregnancy ........................................................................................................ 9
7.1.2. Breastfeeding ................................................................................................ 10
7.1.3. Pediatrics ....................................................................................................... 10
7.1.4. Geriatrics (≥ 65 years of age) ......................................................................... 10
- 8.
Adverse Reactions ......................................................................................................... 10
8.2. Clinical Trial Adverse Reactions .............................................................................. 10
8.5. Post-Market Adverse Reactions ............................................................................. 12
- 9.
Drug Interactions ........................................................................................................... 12
9.3 Drug-Behaviour Interactions ................................................................................... 12
9.4. Drug-Drug Interactions ........................................................................................... 12
9.5. Drug-Food Interactions........................................................................................... 13
9.6. Drug-Herb Interactions ........................................................................................... 13
9.7. Drug-Laboratory Test Interactions ......................................................................... 13
- 10.
Clinical Pharmacology ................................................................................................... 14
10.1. Mechanism of Action .............................................................................................. 14
10.2. Pharmacodynamics ................................................................................................ 14
10.3. Pharmacokinetics ................................................................................................... 15
- 11. Storage, Stability, and Disposal ...................................................................................... 15
Part 2: Scientific Information ................................................................................................ 16
- 13. Pharmaceutical Information .......................................................................................... 16
- 14.
Clinical Trials .................................................................................................................. 17
14.1. Clinical Trials by Indication ..................................................................................... 17
- 16. Non-Clinical Toxicology .................................................................................................. 22
Patient Medication Information ........................................................................................... 24
Part 1: Healthcare Professional Information
1. Indications
RENVELA (sevelamer carbonate) is indicated for:
- the control of hyperphosphatemia in adult and pediatric patients (≥6 years of age and a Body Surface Area (BSA) of ≥0.75 m2) with end-stage renal disease (ESRD) undergoing dialysis
1.1. Pediatrics (6 - <18 years of age)
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of RENVELA has been established in children ≥6 years of age with a BSA ≥0.75 m2 who have ESRD and are undergoing dialysis; therefore, Health Canada has authorized an indication for pediatric use in this population. RENVELA is not recommended for use in children that are below 6 years of age, have a BSA below 0.75 m2, or that have mild hyperphosphatemia (see 7 Warnings and Precautions, Special Populations; 14 Clinical Trials).
1.2. Geriatrics (≥ 65 years of age)
Evidence from clinical studies suggests that lower doses of sevelamer carbonate could be sufficient to normalize serum phosphate levels in elderly patients (≥65 years of age). Cautious monitoring and titration practices are recommended (see 7 Warnings and Precautions, Special Populations; 14 Clinical Trials).
2. Contraindications
RENVELA (sevelamer carbonate) is contraindicated in the following situations:
- patients with hypophosphatemia
- patients with bowel obstruction, or known active mucosal injury such as necrosis, perforation, ulcerative colitis or gastrointestinal bleeding (see 7 Warnings and Precautions).
- patients hypersensitive to sevelamer or one of the other ingredients in the product. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
- Serious cases of dysphagia, bowel obstruction, and perforation, have been associated with RENVELA use, some requiring hospitalization and surgery (see 7 Warnings and Precautions, Gastrointestinal)
4. Dosage and Administration
4.1. Dosing Considerations
- RENVELA (sevelamer carbonate) is available as tablets.
- RENVELA tablets should not be bitten, chewed or broken apart prior to dosing.
- RENVELA should be taken with meals, since its action is to bind ingested phosphate (see 10.1 Mechanism of Action)
- When administering any other medication where a reduction in the bioavailability of that medication would have a clinically significant effect on safety or efficacy, the physician should consider monitoring blood levels or dosing that medicine apart from RENVELA to prevent GI binding (at least one hour before or three hours after RENVELA).
- Monitor serum phosphorus on a regular basis, and adjust the dose of RENVELA based on the desired target range in accordance with current medical standards (see 4.2 Recommended Dose and Dosage Adjustment; Adults, Pediatrics).
- In the pediatric study (see 14 Clinical Trials), children with a BSA ≥0.75 to <1.2 m2 were administered only a powder formulation of sevelamer carbonate. RENVELA is not currently marketed in powder formulation and RENVELA tablets should not be chewed or broken apart. As tablets may present a choking hazard to small children, RENVELA should only be used in pediatric patients who can readily swallow the tablet whole.
4.2. Recommended Dose and Dosage Adjustment
Tablets
RENVELA 800 mg tablets should be taken three times per day with meals at a dosage based on individual patient requirements to control serum phosphate levels (see dosing recommendations for Adults and Pediatrics below).
Adults (≥18 years of age):
The recommended dosing to be used when initiating RENVELA in adult patients not using another phosphate binder is outlined below in Table 1.
Table 1: Starting Dose for Dialysis Patients Not Taking a Phosphate Binder
Initial Serum Phosphorus
RENVELA 800 mg tablet
> 1.8 and < 2.4 mmol/L
1 tablet three times a day with meals
(2.4 grams/day)
≥ 2.4 mmol/L
2 tablets three times a day with meals
(4.8 grams/day)
For patients previously on sevelamer hydrochloride, RENVELA should be given on a gram for gram basis with monitoring of serum phosphorus levels to ensure optimal daily doses.
In a study in 84 chronic kidney disease (CKD) patients on hemodialysis, a similar reduction in serum phosphorus was seen with equivalent doses (approximately mg for mg) of sevelamer hydrochloride and calcium acetate. Table 2 gives recommended starting doses of RENVELA based on a patient’s current calcium acetate dose.
Table 2. Starting Dose for Dialysis Patients Switching From Calcium Acetate to RENVELA
| Calcium Acetate 667 mg (Tablets per meal) | RENVELA 800 mg Tablet (Tablets per meal) |
|---|---|
| 1 tablet | 1 tablet |
| 2 tablets | 2 tablets |
| 3 tablets | 3 tablets |
Dose adjustments, when necessary should be done every 1 to 3 weeks by increasing one tablet per meal (3 tablets per day) until the desired serum levels are met.
The total dose should be divided according to the meal portion during the day.
Pediatric patients (6 - <18 years of age):
The recommended starting dose for pediatric patients is based on the patient’s Body Surface Area (BSA) category (Table 3). The body surface area can be calculated using the Gehan & George body surface area equation:
BSA=0.0235⋅h0.42246⋅w0.51456
BSA is in m2, w is the weight of the person in kg, and h is the height of the person in cm.
RENVELA tablets may present a choking hazard to small children and should not be chewed or broken apart. Therefore, RENVELA should only be used in pediatric patients who can readily swallow the tablet whole.
RENVELA should be taken three times per day with meals and/or snacks. If a pediatric patient eats less than 3 meals/snacks per day, RENVELA should only be given per meal/snack and not on an empty stomach.
| Table 3. Recommended Starting Titration and Dosage based on Pediatric Patient’s Body Surface Area (BSA) (m2) | ||
|---|---|---|
| BSA (m2) | Dose per Meal / Snack | Titration / Comments |
| ≥0.75 to <1.2 | One tablet (800 mg) three times daily | Titrate up /down by one tablet per meal (three tablets per day). RENVELA should only be used in pediatric patients who can readily swallow the tablet whole. |
| ≥1.2 | Two tablets (1.6 g) three times daily | Titrate up / down by one tablet per meal (three tablets per day) |
Perform dose adjustments when necessary according to the BSA category up/down titration dosage quantities listed in Table 3. Titrate in two week intervals for the first 6 weeks, and then every 4 weeks as needed to obtain the desired serum phosphorus target.
In clinical trials, the average actual daily dose of sevelamer carbonate, in adults, was approximately 6 g per day. The highest studied daily dose of sevelamer carbonate taken was 14.4 g per day in adult CKD patients. There was limited clinical trial experience in children with a BSA <1.2 m2 that exceeded 6 g/day and in children with a BSA ≥1.2 m2 that exceeded 10 g/day.
4.4. Administration
Tablets should be swallowed intact and should not be crushed, chewed, or broken into pieces prior to administration.
4.5. Missed Dose
If a dose is forgotten, it should be skipped. Double dosing is not advisable.
5. Overdose
In adult CKD patients on dialysis, the maximum dose studied was 14.4 grams of sevelamer carbonate and 13 grams of sevelamer hydrochloride. Sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, has been given to normal healthy adult volunteers in doses of up to 14.4 grams per day for eight days with no adverse effects. There are no reports of overdosage with sevelamer carbonate or sevelamer hydrochloride in patients. Since sevelamer is not absorbed, the risk of systemic toxicity is low.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-
7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 4 – Dosage Forms, Strengths, and Composition
RENVELA 800 mg tablets are supplied as white to off-white, oval, tablets, engraved with “RV800” on one side, containing 800 mg of sevelamer carbonate on an anhydrous basis, microcrystalline cellulose, sodium chloride, zinc stearate and coating components hypromellose and diacetylated monoglycerides.
RENVELA 800 mg tablets are available in bottles of 180 tablets.
RENVELA tablets are packaged in white high-density polyethylene bottles (HDPE), with a child resistant polypropylene cap and an induction seal.
7. Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
Patients with renal insufficiency may develop hypocalcemia. As RENVELA does not contain calcium, serum calcium levels should be monitored and elemental calcium should be supplemented whenever considered necessary. In cases of hypocalcemia, patients should be given an evening calcium supplement.
Caution should be exercised to avoid hypophosphatemia, a serum phosphorus of < 0.8 mmol/L (see 4 Dosage and Administration).
Rare serious case reports of difficulty swallowing the RENVELA tablet have been reported. Many of these cases involved patients with contributing co-morbid conditions affecting the ability to swallow including swallowing disorders or oesophageal abnormalities. Caution should be exercised when RENVELA tablets are used in these patients.
Sevelamer binds to bile acids and, therefore, prevents cholesterol absorption.
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral | tablet 800 mg of sevelamer carbonate | Diacetylated monoglycerides, hypromellose, microcrystalline cellulose, sodium chloride, zinc stearate. |
The safety and efficacy of RENVELA in patients with renal disease who are not undergoing dialysis has not been established.
Gastrointestinal
Cases of dysphagia and esophageal tablet retention have been reported in association with use of the tablet formulation of RENVELA, some requiring hospitalization and intervention.
Cases of bowel obstruction (ileus, subileus) and perforation have also been reported with RENVELA use. Constipation may be a preceding symptom.
Patients with dysphagia, swallowing disorders, severe gastrointestinal (GI) motility disorders including severe constipation, or major GI tract surgery were not included in the RENVELA clinical studies.
The safety and efficacy of RENVELA in patients with dysphagia, swallowing disorders, severe GI motility disorders including severe constipation, or major GI tract surgery have not been established. Caution should be exercised when RENVELA is used in patients with these GI disorders. These patients should be monitored carefully while being treated with RENVELA. RENVELA treatment should be re-evaluated in patients who develop severe constipation or other severe GI symptoms (see 8 Adverse Reactions).
Cases of serious inflammatory disorders of the gastrointestinal tract (with complications including hemorrhage, perforation, ulceration, necrosis, colitis, and colonic/cecal mass) associated with the presence of sevelamer crystals have been reported (see 8.5 Post-Market Adverse Reactions). Inflammatory disorders may resolve upon RENVELA discontinuation. Treatment discontinuation should be considered in patients who develop severe gastrointestinal symptoms (see 2 Contraindications and 8 Adverse Reactions sections).
Monitoring and Laboratory Tests
Bicarbonate and chloride levels should be monitored. Monitor for reduced vitamins D, E, K and folic acid levels. In preclinical studies in rats and dogs, sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, reduced vitamins D, E and K, and folic acid levels at doses 6-10 times the recommended human dose. In short-term clinical trials, there was no evidence of reduction of serum levels of vitamins. However, in a one-year clinical trial, 25-hydroxyvitamin D (normal range 10 to 55 ng/mL) fell from 39±22 to 34±22 ng/mL (p<0.01) with sevelamer hydrochloride treatment. Most (approximately 75%) patients in sevelamer hydrochloride clinical trials received vitamin supplements which is typical of patients on dialysis.
7.1. Special Populations
7.1.1. Pregnancy
The safety of RENVELA has not been established in pregnant women. In preclinical studies, there was no evidence that sevelamer induced embryolethality, fetotoxicity or teratogenicity at the doses tested (up to 1 g/kg/day in rabbits; up to 4.5 g/kg/day in rats). RENVELA should only be given to pregnant women if the benefits outweigh the risks.
7.1.2. Breastfeeding
There have been no adequate, well-controlled studies in nursing women; however, since sevelamer is not absorbed, excretion in breast milk is not expected.
7.1.3. Pediatrics
The safety and efficacy of RENVELA in pediatrics was evaluated in a clinical trial with hyperphosphatemic children that were ≥6 years of age, had a BSA ≥0.75 m2, and were mostly in ESRD undergoing dialysis. RENVELA was apparently less effective in children with a mildly elevated age-appropriate serum phosphorus level (<2.26 mmol/L), which typically described adolescents not on dialysis at screening (see 14 Clinical Trials). The safety profile in pediatrics was similar to that described for adults (see 8.2 Clinical Trial Adverse Reactions). RENVELA is not recommended for use in children that are below 6 years of age, have a BSA below 0.75 m2, or that have mild hyperphosphatemia. Warnings applicable to adults are also relevant for pediatrics.
Tablets may present a choking hazard to small children. Since RENVELA tablets should not be chewed or broken apart, RENVELA should only be used in pediatric patients who can readily swallow the tablet whole.
7.1.4. Geriatrics (≥ 65 years of age)
In one clinical trial in adults undergoing hemodialysis, patients ≥65 years old (n=5) attained lower serum phosphorus levels compared to patients <65 years old, even if taking lower doses of sevelamer carbonate. Careful monitoring and gradual titration practices are recommended for geriatric patients in order to reduce the risk of hypophosphatemia (see 14 Clinical Trials).
8. Adverse Reactions
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
There are limited data on the safety of RENVELA (sevelamer carbonate). However, because it contains the same active ingredient as the hydrochloride salt, the adverse event profiles of the two salts should be similar. In a cross-over study in patients undergoing hemodialysis with treatment duration of eight weeks each and without a mid-point washout period, the adverse reactions on sevelamer carbonate were similar to those observed on sevelamer hydrochloride.
In long-term studies with sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, the most common adverse events included: vomiting, nausea, diarrhea, dyspepsia, abdominal pain, flatulence and constipation as shown in Table 5. Most frequently occurring treatment related adverse events for RENVELA powder in a short term (4-week cross-over) study were: nausea, constipation and vomiting. During the pediatric study, with the use of sevelamer carbonate tablets and powder, most adverse events reported as related or possibly related to sevelamer carbonate were gastrointestinal in nature. In general, the adverse event profile for the pediatric population evaluated in the study was similar to the profile observed in adults (see 14 Clinical Trials).
Based on studies of 8-52 weeks duration, the most common reasons for discontinuing sevelamer hydrochloride were gastro-intestinal adverse reactions (3-16%).
In a combined safety database comprised of 483 patients with ESRD undergoing hemodialysis, adverse events reported at an incidence ≥10% are provided in Table 5 below. From this database, adverse events are also presented separately from a single long-term randomized clinical study for sevelamer hydrochloride and calcium. The adverse events presented in the table below are not necessarily attributed to sevelamer hydrochloride treatment. The incidence of these events was not dose related.
| Table 5: Adverse Events in Patients with End-Stage Renal Disease undergoing Hemodialysis | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Table 5: Adverse Events in Patients with End-Stage Renal Disease undergoing Hemodialysis | |||||||||
| Total AEs reported | 52 weeks Study of sevelamer hydrochloride vs. calcium (calcium acetate and calcium carbonate) | ||||||||
| Total AEs reported | 52 weeks Study of sevelamer hydrochloride vs. calcium (calcium acetate and calcium carbonate) | ||||||||
System Organ Class Event | sevelamer hydrochloride N = 483 % | sevelamer hydrochloride N = 99 % | calcium N = 101 % | ||||||
System Organ Class Event | sevelamer hydrochloride N = 483 % | sevelamer hydrochloride N = 99 % | calcium N = 101 % | ||||||
Gastrointestinal Disorders Vomiting | 24.4 | 22.2 | 21.8 | ||||||
| Nausea | 25.3 | 20.2 | 19.8 | ||||||
| Diarrhea | 21.1 | 19.2 | 22.8 | ||||||
| Dyspepsia | 15.7 | 16.2 | 6.9 | ||||||
| Constipation | 13.3 | 8.1 | 11.9 | ||||||
Infections and Infestations Nasopharyngitis | 13.9 | 14.1 | 7.9 | ||||||
| Bronchitis | 5.4 | 11.1 | 12.9 | ||||||
| Upper Respiratory Tract Infection | 7.0 | 5.1 | 10.9 | ||||||
Musculoskeletal, Connective Tissue and Bone Disorders Pain in Limb | 13.7 | 13.1 | 14.9 | ||||||
| Arthralgia | 11.4 | 12.1 | 17.8 | ||||||
| Back Pain | 6.0 | 4.0 | 17.8 | ||||||
Skin Disorders Pruritus | 10.4 | 13.1 | 9.9 | ||||||
Respiratory, Thoracic and Mediastinal Disorders Dyspnea | 15.7 | 10.1 | 16.8 | ||||||
| Cough | 11.6 | 7.1 | 12.9 | ||||||
Vascular Disorders Hypertension | 9.3 | 10.1 | 5.9 | ||||||
Nervous System Disorders Headache | 18.4 | 9.1 | 15.8 | ||||||
General Disorders and Site Administration Disorders Dialysis Access Complication | 4.3 | 6.1 | 10.9 | ||||||
| Pyrexia | 8.7 | 5.1 | 10.9 | ||||||
In 143 patients with ESRD undergoing peritoneal dialysis with treatment duration of 12 weeks (97 on sevelamer hydrochloride and 46 on a calcium-based product), the safety profile was similar to that reported for hemodialysis patients except for peritonitis which is a known complication in these patients.
8.5. Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of sevelamer hydrochloride (which has the same active moiety as RENVELA): allergic reactions including angioedema, anaphylaxis (some fatal) and erythema, hypersensitivity vasculitis, pruritus, rash, abdominal pain, fecal impaction, and uncommon cases of intestinal obstruction, ileus, subileus and intestinal perforation. Cases of diverticulitis were also reported.
Cases of serious inflammatory disorders of the gastrointestinal tract (with complications including hemorrhage, perforation, ulceration, necrosis, colitis, and intestinal mass) associated with the presence of sevelamer crystals have been reported (see 2 Contraindications and 7 Warnings and Precautions).
Cases of gastrointestinal mucosal necrosis, gastrointestinal bleeding, and colitis associated with the presence of sevelamer crystals have been reported. However, the causality of the sevelamer crystals in initiating such disorders has not been demonstrated (see 2 Contraindications and 7 Warnings and Precautions sections).
9. Drug Interactions
9.3 Drug-Behaviour Interactions
There have been no adequate, well-controlled studies regarding drug-lifestyle interactions.
9.4. Drug-Drug Interactions
Sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, has been studied in human drug-drug interaction studies. In interaction studies in healthy volunteers, sevelamer hydrochloride had no effect on the bioavailability of a single-dose of digoxin, warfarin, enalapril, metoprolol or iron.
However, the bioavailability of ciprofloxacin was decreased by approximately 50% when co-administered with sevelamer hydrochloride in a single dose study. Consequently, sevelamer hydrochloride (and thus sevelamer carbonate) should not be taken simultaneously with ciprofloxacin.
During postmarketing experience, reduced concentrations of cyclosporin, mycophenolate mofetil and tacrolimus have been reported in transplant patients when co-administered with sevelamer hydrochloride. The possibility of an interaction cannot be excluded and close monitoring of blood concentrations of cyclosporin, mycophenolate mofetil and tacrolimus or dosing these medicines apart from RENVELA to prevent GI binding (at least one hour before or three hours after RENVELA) should be considered during the use of any of these agents in combination with RENVELA and after its withdrawal.
During postmarketing experience, very rare cases of increased thyroid stimulating hormone (TSH) levels have been reported in patients co-administered sevelamer hydrochloride and levothyroxine. Closer monitoring of TSH levels is therefore recommended in patients receiving both medications.
During postmarketing experience, very rare cases of increased phosphate levels have been reported in patients taking proton pump inhibitors co-administered with sevelamer carbonate.
When administering an oral medication where a reduction in the bioavailability of that medication would have a clinically significant effect on its safety or efficacy, the drug should be administered at least one hour before or three hours after sevelamer carbonate, or the physician should consider monitoring blood levels of the drug. Patients taking anti-arrhythmic medications for the control of arrhythmias and anti-seizure medications for the control of seizure disorders were excluded from the clinical trials. Special precautions should be taken when prescribing sevelamer carbonate to patients also taking these medications.
9.5. Drug-Food Interactions
There have been no adequate, well-controlled studies regarding the effect of a variety of foods on the intestinal phosphorus binding of sevelamer. In all clinical studies patients were instructed to take sevelamer with meals.
9.6. Drug-Herb Interactions
There have been no adequate, well-controlled studies regarding drug-herb interactions.
9.7. Drug-Laboratory Test Interactions
There have been no adequate, well-controlled studies regarding drug-laboratory interactions.
10. Clinical Pharmacology
10.1. Mechanism of Action
Sevelamer carbonate is a non-absorbed phosphate binding crosslinked polymer, free of metal and calcium. It contains multiple amines separated by one carbon from the polymer backbone. These amines exist in a protonated form in the intestine and interact with phosphate molecules through ionic and hydrogen bonding. By binding phosphate in the dietary tract and decreasing absorption, sevelamer carbonate lowers the phosphate concentration in the serum.
In addition to effects on serum phosphate levels, sevelamer hydrochloride has been shown to bind bile acids in vitro and in vivo in experimental animal models. Because sevelamer binds bile acids, it may interfere with normal fat absorption and thus may reduce absorption of fat soluble vitamins such as A, D and K as well as other substances such as cholesterol.
In vitro equilibrium studies demonstrated that sevelamer hydrochloride tablets, sevelamer carbonate tablets and sevelamer carbonate powder were equivalent in terms of phosphate binding, with and without acid pre-treatment. Kinetic experiments demonstrated that sevelamer carbonate and sevelamer hydrochloride tablets bind phosphate in a similarly rapid manner. Therefore, these in vitro studies have shown that sevelamer carbonate and sevelamer hydrochloride are equivalent in their phosphate binding properties.
Sevelamer does not contain calcium and decreases the incidence of hypercalcaemic episodes as compared to patients using calcium based phosphate binders alone. The effects of sevelamer on phosphorus and calcium were proven to be maintained throughout a study with one year follow-up.
Patients with chronic kidney disease (CKD) retain phosphorus and can develop hyperphosphatemia. High serum phosphorus can precipitate serum calcium resulting in ectopic calcification. When the product serum calcium and phosphorus concentrations (Ca x P) exceeds 4.4 mmol/L, there is an increased risk that ectopic calcification will occur. Hyperphosphatemia plays a role in the development of secondary hyperparathyroidism in renal insufficiency. An increase in parathyroid hormone (PTH) levels is characteristic of patients with chronic renal failure. Increased levels of PTH can lead to osteitis fibrosa. A decrease in serum phosphorus may decrease serum PTH levels.
10.2. Pharmacodynamics
Several in vitro assays and animal models were employed to evaluate the activity and efficacy of sevelamer. In vitro equilibrium and kinetic binding studies comparing sevelamer hydrochloride tablets (800 mg), sevelamer carbonate tablets (800 mg), and sevelamer carbonate powder (0.8 g, 1.6 g, and 2.4 g sachets) were conducted to compare key parameters of phosphate binding under varying physiologically relevant conditions that might be encountered in the gastrointestinal tract. This included varying concentrations of phosphate with and without acid pre-treatment.
Administration of sevelamer to normal rats produced 90 and 77% increases in fecal excretion of phosphorus in the two experiments. Calcium carbonate produced a 23% increase in fecal phosphorus excretion compared to a 77% increase produced by sevelamer. Decreased urinary phosphorus, indicating decreased absorption of phosphorus was observed in a dose-dependant manner with sevelamer administration. Animals administered a 0.5% dietary mixture had a 57% decrease in total urinary phosphorus, while animals administered 1, 3 and 9% had 66, 88 and 96% decreases in total urinary phosphorus, respectively. The results from these efficacy studies demonstrate that sevelamer is capable of binding dietary phosphorus in normal animals, preventing GI absorption of phosphorus.
10.3. Pharmacokinetics
Pharmacokinetic studies have not been carried out with sevelamer carbonate or sevelamer hydrochloride as sevelamer is not absorbed from the GI tract, as confirmed by an absorption study in healthy volunteers. In this study a mass balance study using 14C-sevelamer hydrochloride in 16 healthy male and female volunteers showed that sevelamer hydrochloride is not systemically absorbed. No absorption studies have been performed in patients with renal disease.
- 11. Storage, Stability, and Disposal
Store at controlled room temperature 15°C to 30°C. Protect from moisture and heat.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Sevelamer carbonate (USAN)
Chemical names:
- 1. poly(allylamine-co-N,N’-diallyl-1,3-diamino-2-hydroxypropane) carbonate salt (CAS)
- 2. Oxirane, (chloromethyl)-, polymer with 2-propen-1-amine, carbonate salt (CAS)
- 3. 2-Propen-1-amine, polymer with (chloromethyl) oxirane, carbonate salt (CAS)
- 4. Allylamine polymer with 1-chloro-2,3-epoxypropane, carbonate salt (IUPAC)
Molecular formula: (C3H7N•nH2CO3)810z(C9H18N2O•nH2CO3)95z where z = a large number.
Sevelamer carbonate is a highly cross-linked polymer of varying size, and each particle can be considered as one molecule. Since the molecular weight is equal to the weight of the particle itself, the molecular weight distribution of a cross-linked polymer is a function of the distribution of particle sizes.
Structural formula:
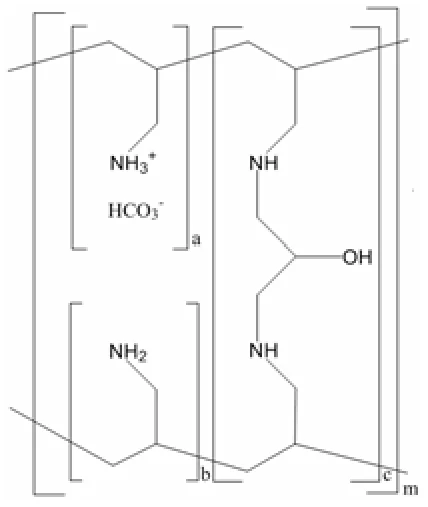
a, b = number of primary amine groups a + b = 9 c = number of crosslinking groups c = 1 m = large number to indicate extended polymer network
Physicochemical properties:
Description: Sevelamer carbonate is a cross-linked poly(allylamine carbonate) polymer. The cross-linking agent is epichlorohydrin (1-chloro-2,3-epoxypropane). The cross-linking groups consist of two secondary amine groups derived from the starting material, poly(allylamine hydrochloride) and one molecule of epichlorohydrin giving 2-hydroxypropyl linkers. A portion of the amine is present as the carbonate salt, at 14 – 21% by weight; this is similar to sevelamer hydrochloride where the chloride salt is present at 15 – 20%, by weight.
Physical Form: White to off-white free flowing powder.
Solubilities: Insoluble in all tested solvents.
Crystallinity: Amorphous, granular.
pH Values: 8 – 10.5 (1% aqueous slurry).
Hygroscopicity: Sevelamer carbonate is hygroscopic.
14. Clinical Trials
14.1. Clinical Trials by Indication
The safety and efficacy of sevelamer to control serum phosphorus in CKD patients on dialysis was mainly determined by the ability of sevelamer hydrochloride to bind phosphorus from food in one double-blind and several open-label clinical trials in hemodialysis and peritoneal dialysis patients. Both tablet and powder formulations of sevelamer carbonate administered three times per day with meals have been shown to control serum phosphorus effectively.
In two double-blind, randomized, two 8-week period cross-over clinical trials in hemodialysis patients, sevelamer carbonate was shown to be therapeutically equivalent to sevelamer hydrochloride.
In the first study, 79 stage 5 CKD patients received, in a random order, sevelamer carbonate 800 mg tablet and sevelamer hydrochloride 800 mg tablets during each 8-week period without an intervening washout phase. The study dose during the cross-over period was based on the sevelamer hydrochloride given during the run-in period. The average actual dose divided among meals during the randomized treatment periods was 6.0 ± 2.8 g/day for both treatment regimens. There was no significant difference in mean serum phosphorus between the two groups during the treatment periods (1.5 ± 0.3 mmol/l during sevelamer carbonate treatment and 1.5±0.3 mmol/l during sevelamer hydrochloride treatment). Following a two-week washout phase after the end of the last period of the cross-over, phosphorus rose significantly to 2.1 ± 0.6 mmol/l.
In the second study, 21 hyperphosphatemic patients with CKD receiving hemodialysis 3 times per week received, in a random order, sevelamer hydrochloride tablets 800 mg and sevelamer carbonate powder 800 mg, each during a 4-week period without an intervening washout phase. The study dose during the cross-over period was based on the dose of sevelamer hydrochloride given during the run-in period. The average actual daily dose (divided between meals) administered during the randomized treatment periods was 5.9 ± 2.7 g for sevelamer carbonate powder and 6.5 ± 3.3 g for sevelamer hydrochloride tablets. This study demonstrated that sevelamer carbonate powder dosed three times per day with meals was equivalent in controlling serum phosphorus levels in hyperphosphatemic adults to sevelamer hydrochloride tablets dosed three times per day with meals (serum phosphorus time weighted averages were 1.6 ± 0.5 mmol/L for sevelamer carbonate powder and 1.7 ± 0.4 mmol/L for sevelamer hydrochloride tablets).
The ability of sevelamer hydrochloride to lower serum phosphorus in CKD patients on dialysis was demonstrated in six clinical trials: one double-blind placebo controlled 2-week study (sevelamer hydrochloride N=24); two open-label uncontrolled 8-week studies (sevelamer hydrochloride N=220) and three active-controlled open-label studies with treatment durations of 8 to 52 weeks (sevelamer hydrochloride N=256). Three of the active-controlled studies are described here. One is a crossover study with two 8-week periods comparing sevelamer hydrochloride to an active-control. The second is a 52-week parallel study comparing sevelamer hydrochloride with active-control. The third is a 12-week parallel study comparing sevelamer hydrochloride and active-control in peritoneal dialysis patients.
Hemodialysis Patients
Active-Control, Cross-Over Study in Hemodialysis Patients
Eighty-four CKD patients on hemodialysis who were hyperphosphatemic (serum phosphorus > 1.9 mmol/L) following a two-week phosphate binder washout period received sevelamer and active-control for eight weeks each in random order. Treatment periods were separated by a two-week phosphate binder washout period. Patients started on treatment three times per day with meals. Over each eight-week treatment period, at three separate time points the dose of sevelamer could be titrated up 1 capsule or tablet per meal (3 per day) to control serum phosphorus, the dose of active-control could also be altered to attain phosphate control. Both treatments significantly decreased mean serum phosphorus by about 0.6 mmol/L (Table 6).
| Table 6 Mean Serum Phosphorus (mmol/L) at Baseline and Endpoint | ||||||
| Sevelamer Hydrochloride (N=81) | Active Control (N=83) | |||||
| Baseline at End of Washout | 2.7 | 2.6 | ||||
| Endpoint | 2.1 | 1.9 | ||||
| Change from Baseline at Endpoint (95% Confidence Interval) | -0.6* (-0.8, -0.5) | -0.7* (-0.8, -0.5) | ||||
| *p<0.0001, within treatment group comparison | ||||||
The distribution of responses is shown in Figure 1. The distributions are similar for sevelamer hydrochloride and active control. The median response is a reduction of about 0.6 mmol/L in both groups. About 50% of subjects have reductions between 0.3 and 1.0 mmol/L.
Figure 1. Percentage of patients (Y-axis) attaining a phosphorus reduction from baseline (mmol/L) at least as great as the value of the X-axis.
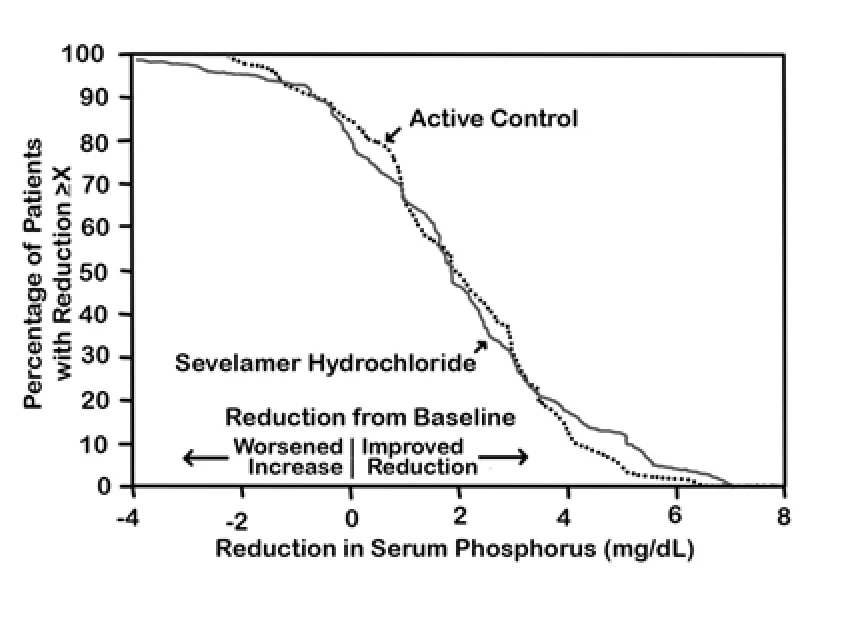
-1.3 -0.6 0 0.6 1.3 1.9 2.6
Reduction in Serum Phosphorus (mmol/L)
Average daily sevelamer hydrochloride dose at the end of treatment was 4.9 g (range of 0.0 to 12.6 g).
Active-Control, Parallel Study in Hemodialysis Patients
Two hundred CKD patients on hemodialysis who were hyperphosphatemic (serum phosphorus >1.8 mmol/L) following a two-week phosphate binder washout period were randomized to receive sevelamer hydrochloride 800 mg tablets (N=99) or an active-control (N=101). The two treatments produced similar decreases in serum phosphorus. At week 52, using last-observation-carried-forward, sevelamer hydrochloride and active-control both significantly decreased mean serum phosphorus (Table 7).
| Table 7. Mean Serum Phosphorus (mmol/L) and Ion at Baseline and Change from Baseline to End of Treatment | ||||
Sevelamer HCl (N=94) | Active-Control (N=98) | |||
| Phosphorus Baseline | 2.4 | 2.4 | ||
| Change from Baseline at Endpoint | -0.7 | -0.6 | ||
Ca x Phosphorus Ion Product Baseline | 5.7 | 5.5 | ||
Change from Baseline at Endpoint | -1.6 | -1.1 | ||
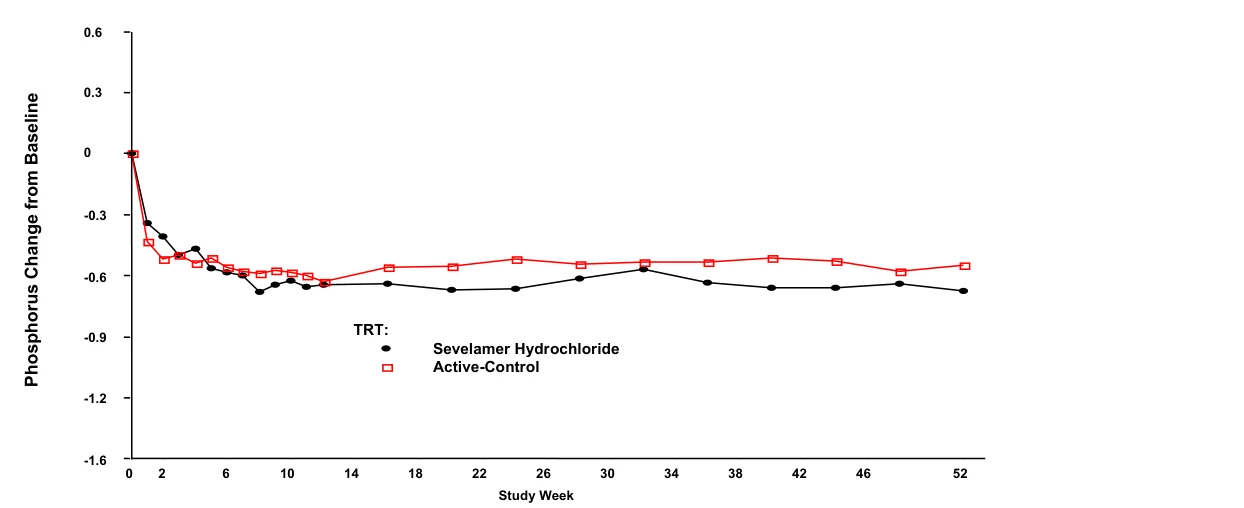
Sixty-one percent of sevelamer hydrochloride patients and 73% of the control patients completed the full 52 weeks of treatment. Figure 2, a plot of the phosphorus change from baseline for the completers, illustrates the durability of response for patients who are able to remain on treatment.
Figure 2. Mean Phosphorus Change from Baseline for Patients who Completed 52 Weeks of Treatment
Average daily sevelamer hydrochloride dose at the end of treatment was 6.5 g (range of 0.8 to 13 g).
Active-Control, Parallel Study in Peritoneal Dialysis Patients
One hundred and forty-three patients on peritoneal dialysis who were hyperphosphatemic (serum phosphorus > 1.8 mmol/L) following a two-week phosphate binder washout period were randomized to receive sevelamer hydrochloride (N=97) or active-control (N=46) open label for 12 weeks. Average daily sevelamer hydrochloride dose at the end of treatment was 5.9 g (range 0.8 to 14.3 g). There were statistically significant changes in serum phosphorus (p<0.001) for sevelamer hydrochloride (-0.5 mmol/L from baseline of 2.4 mmol/L), similar to the active-control.
Clinical Study of Sevelamer Carbonate Powder and Tablets in Pediatric Patients
The safety and efficacy of sevelamer carbonate in hyperphosphatemic pediatric patients with Chronic Kidney Disease (CKD) was evaluated in a multicenter study with a 2-week, randomized, placebo-controlled, Fixed Dose Period (FDP) followed by a 6-month, single-arm, open-label, Dose Titration Period (DTP). A total of 101 patients (6 to 18 years old) with a Body Surface Area (BSA) range of 0.8 m2 to 2.4 m2 and hyperphosphatemia secondary to CKD were randomized in the study. Most patients were 13 to 18 years of age (73%), had a BSA ≥1.2 m2 (84%), and were in ESRD (78%) undergoing dialysis (77%). Forty-nine (49) patients received sevelamer carbonate and 51 patients received placebo during the 2 week FDP; thereafter all patients received sevelamer carbonate for the 26-week Dose Titration Period (DTP).
The study met its primary and secondary efficacy endpoints. As the primary efficacy endpoint, sevelamer carbonate significantly reduced serum phosphorus through Week 2 of the FDP by an LS Mean difference of -0.29 (SE 0.087) mmol/L compared to placebo (p=0.001). The treatment response during the 2-week FDP was not affected by BSA. In contrast, no treatment response was observed in patients with a baseline serum phosphorus below 2.26 mmol/L or in patients that were not on dialysis (Figure 3). A similar treatment response was observed in patients who received sevelamer carbonate during the 6-month open-label DTP At the end of the DTP (week 28), 27% of patients on sevelamer carbonate reached their age-appropriate normal serum phosphorus levels, and children with a BSA <1.2 m2 and a BSA ≥1.2 m2 were prescribed a mean daily dose of approximately 4 g and 7 g, respectively. Most of the treatment emergent adverse events reported as related, or possibly related to sevelamer carbonate were gastrointestinal disorders such as nausea, constipation, vomiting, and abdominal pain. No new safety signals were identified during the study.
Figure 3. Change in Serum Phosphorus (mmol/L) from Baseline to Week 2 of the FDP by Subgroup
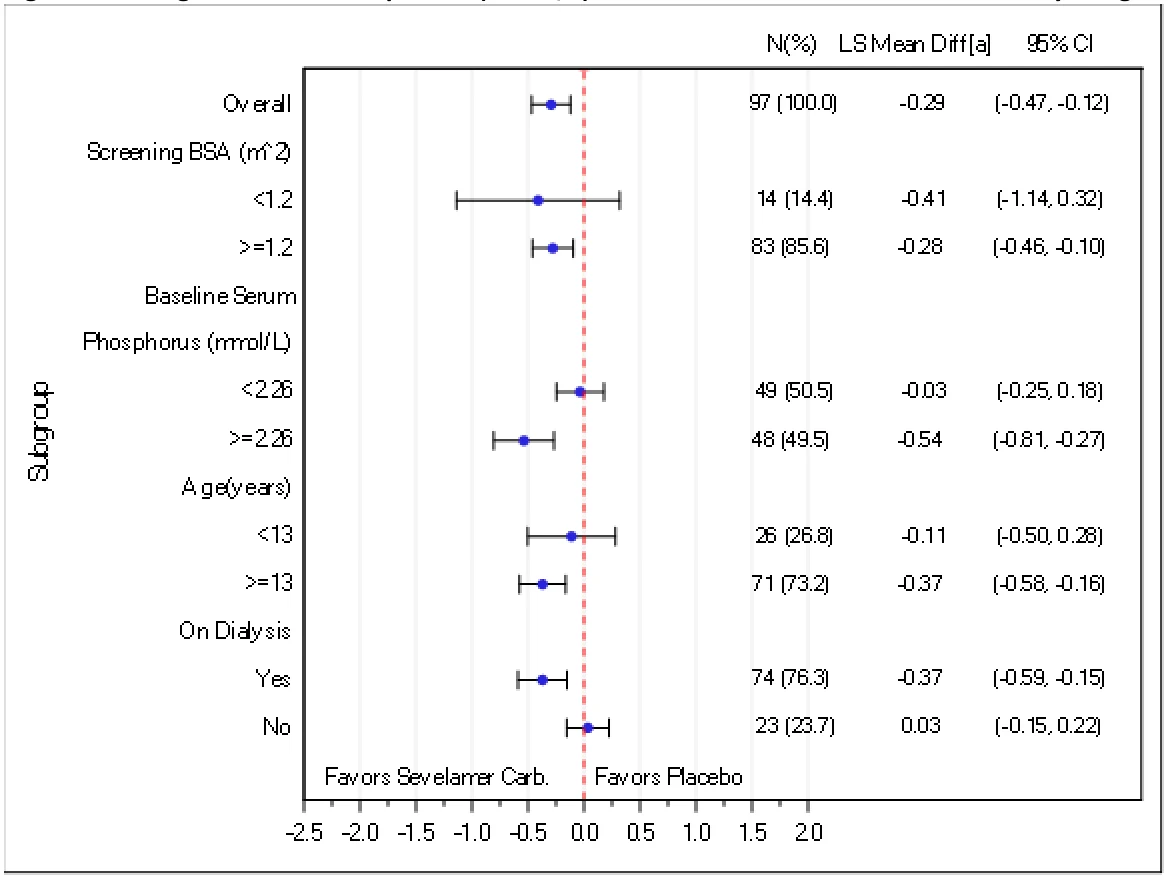
Note: LS Mean difference of Sevelamer Carbonate – Placebo, based on ANCOVA within subgroup and with treatment as fixed effect and screening BSA and baseline serum phosphorus as covariates.
16. Non-Clinical Toxicology
General toxicology:
RENVELA contains sevelamer, a non-absorbed phosphate binding crosslinked polymer, free of metal and calcium. RENVELA (sevelamer carbonate) was developed as a pharmaceutical alternative to sevelamer hydrochloride (RENAGEL®).
Both sevelamer hydrochloride and sevelamer carbonate salt forms are polymeric anion exchange resins with the same polymeric structure. The amines in the polymer exist in a protonated form and bind to negatively charged phosphates. While the counterions differ for the two salts, the polymer itself, the active moiety responsible for binding of phosphate, remains the same. Since in both resins the active moiety responsible for phosphate binding is the same polymer (sevelamer) and the two salts have been shown to be equivalent both in in vitro and in vivo, the nonclinical data generated using sevelamer hydrochloride are also applicable to sevelamer carbonate.
To assess nonclinical toxicity, sevelamer was administered orally to Sprague-Dawley rats acutely and for 1, 3, and 6 months at doses up to 10 g/kg/day, and to beagle dogs acutely and for 1, 3, and 12 months at doses up to 2 g/kg/day. In general, sevelamer caused minimal toxicity. In rats, sevelamer produced a dose-dependent decrease in fat-soluble vitamin E and decreased levels of fat-soluble vitamin D and vitamin K (measured by coagulation time) at high doses only. Potentially clinically relevant findings (anemia, focal hemorrhages) due to these decreased serum fat-soluble vitamin levels have only been observed in high-dose (4.5 to 10 g/kg/day) male rats.
In the segment II studies in rats and rabbits, there was no evidence that sevelamer directly induced embryolethality, fetotoxicity, or teratogenicity at the highest doses tested (1.0 g/kg/day in rabbits and 4.5 g/kg/day in rats). In rats, at doses of 1.5 and 4.5 g/kg/day (approximately 8 and 20 times the maximum clinical trial dose of 200 mg/kg/day), sevelamer caused reduced or irregular ossification of fetal bones, probably due to a reduced absorption of fat-soluble vitamin D and/or vitamin K depletion at these high doses.
Sevelamer has not been studied in juvenile animals. Its effects on pediatric development are inferred from short-term pediatric clinical studies (see 14 Clinical Trials, Clinical Study of Sevelamer Carbonate Powder and Tablets in Pediatric Patients).
There are no reported overdoses of sevelamer in patients. Since sevelamer is not absorbed, the risk of systemic toxicity is low.
Studies were conducted with sevelamer carbonate to bridge from the existing toxicology for the hydrochloride salt of sevelamer to the carbonate salt.
To assess nonclinical toxicity, sevelamer hydrochloride and sevelamer carbonate were administered to Sprague Dawley rats and to beagle dogs for four weeks. In rats, two groups received diet mixed with sevelamer carbonate at the dose-level of 1.0 or 4.5 g/kg/day and two other groups received diet mixed with sevelamer hydrochloride at the dose-level of 1.0 or 4.5 g/kg/day. In dogs, treated animals received either sevelamer carbonate or sevelamer hydrochloride once daily by oral gavage at a dose level of 0.2 or 1.0 g/kg/day. Other than the reduced serum levels of fat soluble vitamins in rats, no systemic toxicity related to administration of sevelamer carbonate or sevelamer hydrochloride was observed. In addition, these findings were comparable to those seen with similar studies conducted with sevelamer hydrochloride.
Genotoxicity:
A series of genotoxicity studies were performed to assess sevelamer’s mutagenic potential. In the Salmonella typhimurium reverse mutation assay, sevelamer produced the same mean number of revertants as the negative control in all strains tested with and without metabolic activation. Sevelamer is considered to be non-mutagenic. In the in vitro mammalian cytogenetics test, sevelamer, at 5 mg/mL, was concluded to be weakly positive for the induction of structural chromosome aberrations and negative for the induction of numerical chromosome aberrations. The weakly positive effects of sevelamer are thought to be due to sevelamer’s ability to absorb the culture medium and not the direct action of the test article. Sevelamer was tested in the in vivo mouse micronucleus assay to confirm these results. Since sevelamer is non-absorbed, it was injected intraperitoneally to maximize its potential effects. Sevelamer was administered at doses up to 5 g/kg/day for 2 consecutive days. Under the conditions of this study, sevelamer was concluded to be nonclastogenic.
Carcinogenicity:
Standard lifetime carcinogenicity bioassays were conducted in mice and rats. Rats were given sevelamer hydrochloride by diet at 0.3, 1, or 3 g/kg/day. There was an increased incidence of urinary bladder transitional cell papilloma in male rats (3 g/kg/day) at a human equivalent dose 2 times the maximum clinical trial dose of 14.4 g/day. Mice received mean dietary doses of 0.8, 3, or 9 g/kg/day. No increased incidence of tumors was observed in mice at a human equivalent dose 3 times the maximum clinical trial dose of 14.4 g/day.
Reproductive and developmental toxicology:
Developmental and reproductive toxicity studies have been performed with sevelamer to assess teratogenic potential and effects on fertility. In the segment I study, sevelamer had no adverse effect upon male and female fertility or on early embryonic development at the highest dose tested (4.5 g/kg/day). In the segment III pre- and post-natal study, there was no evidence of maternal toxicity at any dose level. There was no effect on reproductive performance during gestation, parturition or lactation and no effect on the survival, physical development, behavior and reproductive performance of the F1 generation or on the survival and development of the F2 generation pups at doses tested (≤ 1.0 g/kg/day). In conclusion, no reproductive toxicity has been observed with sevelamer.