


Product Monograph - Rifapentine Tablets
Recent Major Label Changes
| None at time of most recent authorization |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................................ 2
Table of Contents ................................................................................................................................. 2
Part 1: Health Professional Information ............................................................................................... 4
1 Indications ............................................................................................................................... 4
1.1 Pediatrics .................................................................................................................................... 4
1.2 Geriatrics .................................................................................................................................... 4
2 Contraindications .................................................................................................................... 4
4 Dosage and Administration ..................................................................................................... 5
4.1 Dosing Considerations ............................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .......................................................................... 5
4.4 Administration ........................................................................................................................... 5
4.5 Missed Dose ............................................................................................................................... 5
5 Overdose ................................................................................................................................. 6
6 Dosage Forms, Strengths, Composition and Packaging ............................................................. 6
7 Warnings and Precautions ....................................................................................................... 6
General ............................................................................................................................................. 6
Carcinogenesis and Mutagenesis ..................................................................................................... 7
Endocrine and Metabolism .............................................................................................................. 7
Gastrointestinal ................................................................................................................................ 7
Hepatic/Biliary/Pancreatic ............................................................................................................... 7
Immune ............................................................................................................................................ 8
Monitoring and Laboratory Tests .................................................................................................... 8
Reproductive Health ........................................................................................................................ 8
Sensitivity/Resistance ...................................................................................................................... 8
Skin ................................................................................................................................................... 8
7.1 Special Populations .................................................................................................................... 9
7.1.1 Pregnancy ....................................................................................................................... 9
7.1.2 Breastfeeding ................................................................................................................. 9
7.1.3 Pediatrics ........................................................................................................................ 9
7.1.4 Geriatrics ...................................................................................................................... 10
8 Adverse Reactions ................................................................................................................. 10
8.2 Clinical Trial Adverse Reactions ............................................................................................... 10
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................................ 11
8.3 Less Common Clinical Trial Adverse Reactions ........................................................................ 12
8.5 Post-Market Adverse Reactions ............................................................................................... 12
9 Drug Interactions ................................................................................................................... 12
9.3 Drug-Behaviour Interactions .................................................................................................... 12
9.4 Drug-Drug Interactions ............................................................................................................ 12
9.5 Drug-Food Interactions ............................................................................................................ 14
9.6 Drug-Herb Interactions ............................................................................................................ 14
9.7 Drug-Laboratory Test Interactions ........................................................................................... 14
10 Clinical Pharmacology ............................................................................................................ 15
10.1 Mechanism of Action ............................................................................................................. 15
10.3 Pharmacokinetics ................................................................................................................... 15
11 Storage, Stability and Disposal ............................................................................................... 18
Part 2: Scientific Information ............................................................................................................. 19
13 Pharmaceutical Information .................................................................................................. 19
14 Clinical Trials ......................................................................................................................... 19
14.1 Clinical Trials by Indication ..................................................................................................... 19
14.2 Comparative Bioavailability Studies ....................................................................................... 20
15 Microbiology ......................................................................................................................... 22
16 Non-Clinical Toxicology .......................................................................................................... 23
Patient Medication Information ......................................................................................................... 25
Part 1: Health Professional Information
1 Indications
RIFAPENTINE TABLETS (rifapentine) are indicated for:
- the treatment of latent tuberculosis infection (LTBI) caused by Mycobacterium tuberculosis in combination with isoniazid in patients 2 years of age and older at high risk of progression to tuberculosis disease.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of RIFAPENTINE TABLETS and other antibacterial drugs, RIFAPENTINE TABLETS should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Limitations of Use
Active tuberculosis disease should be ruled out before initiating treatment for LTBI.
RIFAPENTINE TABLETS must always be used in combination with isoniazid as a 12-week once-weekly regimen for the treatment of LTBI (see 4 Dosage and Administration).
RIFAPENTINE TABLETS in combination with isoniazid is not recommended for individuals presumed to be exposed to rifamycin-resistant or isoniazid-resistant M. tuberculosis.
1.1 Pediatrics
Pediatrics (age 2 to <18 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of RIFAPENTINE TABLETS in pediatric patients has been established. Therefore Health Canada has authorized an indication for pediatric use (see 7.1.3 Pediatrics, 8.2.1 Clinical Trial Adverse Reactions - Pediatrics and 10.3 Pharmacokinetics).
1.2 Geriatrics
Geriatric (≥65 years of age): A limited number of patients aged 65 years and over have been treated in clinical studies. The use in geriatric populations may be associated with differences in safety or effectiveness (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
2 Contraindications
- RIFAPENTINE TABLETS are contraindicated in patients who are hypersensitive to this drug, have a history of a previous hypersensitivity reaction to any of the rifamycins or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
4 Dosage and Administration
4.1 Dosing Considerations
- RIFAPENTINE TABLETS should be administered once weekly in combination with isoniazid for 12 weeks as directly observed therapy. For more information on the use of isoniazid, refer to isoniazid Product Monograph.
4.2 Recommended Dose and Dosage Adjustment
- Adults and children 12 years and older: The recommended dose of RIFAPENTINE TABLETS should be determined based on weight of the patient up to a maximum of 900 mg once weekly (see Table 1). The recommended dose of isoniazid is 15 mg/kg (rounded to the nearest 50 mg or 100 mg) up to a maximum of 900 mg once weekly for 12 weeks.
Children 2 to 11 years: The recommended dose of RIFAPENTINE TABLETS should be determined based on weight of the patient up to a maximum of 900 mg once weekly (see Table 1). The recommended dose of isoniazid is 25 mg/kg (rounded to the nearest 50 mg or 100 mg) up to a maximum of 900 mg once weekly for 12 weeks.
Table 1: Weight Based Dose of Rifapentine in the Treatment of Latent Tuberculosis Infection
| Weight range | RIFAPENTINE TABLETS dose | Number of RIFAPENTINE TABLETS |
|---|---|---|
| 10-14 kg | 300 mg | 2 |
| 14.1-25 kg | 450 mg | 3 |
| 25.1-32 kg | 600 mg | 4 |
| 32.1-50 kg | 750 mg | 5 |
| >50 kg | 900 mg | 6 |
4.4 Administration
- RIFAPENTINE TABLETS should be taken with meals. Administration of RIFAPENTINE TABLETS with a meal increases oral bioavailability and may reduce the incidence of gastrointestinal upset, nausea, and/or vomiting (see 9.5 Drug-Food Interactions and 10.3 Pharmacokinetics)
- For patients who cannot swallow tablets, the tablets may be crushed and added to a small amount of semi-solid food, all of which should be consumed immediately (see 10.3 Pharmacokinetics).
4.5 Missed Dose
A missed dose can be administered on the next available day during the same week, as long as the minimum timeframe of 72 hours between the doses is complied with and no more than 5 doses are administered over a period of 28 days.
5 Overdose
While there is no experience with the treatment of acute overdose with RIFAPENTINE TABLETS, clinical experience with rifamycins suggests that gastric lavage to evacuate gastric contents (within a few hours of overdose), followed by instillation of an activated charcoal slurry into the stomach, may help adsorb any remaining drug from the gastrointestinal tract.
Rifapentine and 25-desacetyl rifapentine are highly plasma protein bound. Rifapentine and related compounds excreted in urine account for only 17% of the administered dose, therefore, neither hemodialysis nor forced diuresis is expected to enhance the systemic elimination of unchanged rifapentine from the body of a patient with RIFAPENTINE TABLETS overdose.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844-POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition and Packaging
Table 2 – Dosage Forms, Strengths and Composition
RIFAPENTINE TABLETS is a film coated tablet.
Description
RIFAPENTINE TABLETS are supplied as 150 mg reddish brown colored, round, beveled edge, biconvex, film-coated tablets debossed with "K" and "23" on one side and plain on other side.
They are available in blister pack and strip pack.
Carton of 24 tablets (3 packs of 8 tablets in peel push blisters)
Carton of 48 tablets (6 packs of 8 tablets in peelable blisters)
Carton of 70 tablets (7 blisters of 10 tablets)
7 Warnings and Precautions
General
Discolouration of Body Fluids and Tissues
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients |
| Oral | Tablet 150 mg | Calcium stearate, colloidal silicon dioxide, disodium EDTA, hydroxypropyl cellulose, iron oxide red, low substituted hydroxypropyl cellulose, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol - part hydrolyzed, pregelatinized starch, sodium ascorbate, sodium lauryl sulfate, sodium starch glycolate, talc and titanium dioxide. |
RIFAPENTINE TABLETS may produce a red-orange discoloration of body tissues and/or fluids (e.g., skin, teeth, tongue, urine, feces, saliva, sputum, tears, sweat, and cerebrospinal fluid). Contact lenses or dentures may become permanently stained.
Carcinogenesis and Mutagenesis
See 16 Non-Clinical Toxicology.
Endocrine and Metabolism
Drug interactions
Rifapentine is an inducer of CYP450 enzymes. Concomitant use of rifapentine with other drugs metabolized by these enzymes, such as protease inhibitors, certain reverse transcriptase inhibitors, and hormonal contraception may cause a significant decrease in plasma concentrations and loss of therapeutic effect (see 9.4 Drug-Drug Interactions).
Porphyria
Porphyria has been reported in patients receiving rifampin, attributed to induction of delta amino levulinic acid synthetase. Because rifapentine may have similar enzyme induction properties, avoid the use of rifapentine in patients with porphyria.
Gastrointestinal
Clostridioides Difficile-Associated Disease
Clostridioides difficile–associated disease (CDAD) has been reported with use of many antibacterial agents, including rifapentine. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridioides difficile. C. difficile produces toxins A and B which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridioides difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridioides difficile. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases.
Hepatic/Biliary/Pancreatic
Hepatotoxicity
Elevations of liver transaminases may occur in patients receiving rifapentine (see 8.2 Clinical Trial Adverse Reactions). Patients on RIFAPENTINE TABLETS should be monitored for symptoms of liver injury.
Patients with abnormal liver tests and/or liver disease should only be given RIFAPENTINE TABLETS in cases of necessity and under strict medical supervision. In such patients, obtain serum transaminase levels prior to therapy and every 2 to 4 weeks while on therapy. Discontinue RIFAPENTINE TABLETS if evidence of liver injury occurs.
Immune
Hypersensitivity and Related Reactions
Hypersensitivity reactions may occur in patients receiving RIFAPENTINE TABLETS. Signs and symptoms of these reactions may include hypotension, urticaria, angioedema, acute bronchospasm, conjunctivitis, thrombocytopenia, neutropenia or flu-like syndrome (weakness, fatigue, muscle pain, nausea, vomiting, headache, fever, chills, aches, rash, itching, sweats, dizziness, shortness of breath, chest pain, cough, syncope, palpitations). There have been reports of anaphylaxis.
Monitor patients receiving rifapentine therapy for signs and/or symptoms of hypersensitivity reactions. If these symptoms occur, administer supportive measures and discontinue RIFAPENTINE TABLETS.
Monitoring and Laboratory Tests
Therapeutic concentrations of rifampin have been shown to inhibit standard microbiological assays for serum folate and Vitamin B12. Similar drug-laboratory interactions should be considered for RIFAPENTINE TABLETS; thus, alternative assay methods should be considered (see 9.7 Drug-Laboratory Test Interactions).
Reproductive Health
Contraception
Use of rifapentine may reduce the efficacy of hormonal contraceptives. Patients using hormonal contraceptives should use an alternative non-hormonal contraceptive method or add a barrier method of contraception during treatment with RIFAPENTINE TABLETS (see 7.1.1 Pregnancy, 9.4 Drug-Drug Interactions, and 16 Non-Clinical Toxicology).
Sensitivity/Resistance
Development of Drug Resistant Bacteria
Prescribing RIFAPENTINE TABLETS in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Skin
Severe Cutaneous Adverse Reactions
Severe cutaneous adverse reactions (SCARs) such as Stevens-Johnson syndrome (SJS) and drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome have been reported in association with the use of rifapentine treatment regimens in patients with active and latent tuberculosis. Discontinue RIFAPENTINE TABLETS at the first appearance of skin rash, mucosal lesions, or any other sign of hypersensitivity (see 7 Warnings and Precautions, Immune).
7.1 Special Populations
7.1.1 Pregnancy
There is limited data examining rifapentine use during pregnancy in clinical trials. However, based on animal data, patients who are pregnant or who could become pregnant while taking rifapentine should be advised of the risk of fetal harm. RIFAPENTINE TABLETS should only be used during pregnancy if the potential benefit justifies the potential risk to the fetus.
In animal reproduction and developmental toxicity studies, rifapentine produced fetal harm and was teratogenic in rats and rabbits at doses approximately 0.3 to 1.3 times a single human dose of 600 mg based on body surface area comparisons (see 16 Non-Clinical Toxicology).
Disease-associated maternal and/or embryo-fetal risk
Active tuberculosis in pregnancy is associated with adverse maternal and neonatal outcomes including maternal anemia, cesarean delivery, preterm birth, low birth weight, birth asphyxia and perinatal infant death.
Labor and/or delivery
When administered during the last few weeks of pregnancy, RIFAPENTINE TABLETS may increase the risk for maternal postpartum hemorrhage and bleeding in the exposed neonate. Monitor prothrombin time of pregnant women and neonates who are exposed to RIFAPENTINE TABLETS during the last few weeks of pregnancy. Treatment with Vitamin K may be indicated.
7.1.2 Breastfeeding
There are no data on the presence of rifapentine or its metabolite in human or animal milk, the effects on the breastfed infant, or the effects on milk production. Since RIFAPENTINE TABLETS may produce a red-orange discoloration of body fluids, there is a potential for discoloration of breast milk.
Monitor infants exposed to rifapentine through breast milk for signs of hepatotoxicity, including irritability, prolonged unexplained crying, yellowing of the eyes, loss of appetite, vomiting, and changes in color of the urine (darkening) or stool (lightening, pale or light brown). The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for RIFAPENTINE TABLETS and any potential adverse effects on the breastfed infant from RIFAPENTINE TABLETS or from the underlying maternal condition.
7.1.3 Pediatrics
The safety and effectiveness of rifapentine in combination with isoniazid once-weekly regimen has been evaluated in pediatric patients (2 to <18 years of age) for the treatment of latent tuberculosis infection. In clinical studies, the safety profile in children was similar to that observed in adult patients (see 8.2.1 Clinical Trial Adverse Reactions – Pediatrics and 14.1 Clinical Trials by Indication).
In a pharmacokinetic study conducted in 2 to 11-year-old pediatric patients with latent tuberculosis infection, rifapentine was administered once weekly based on weight (15 mg/kg to 30 mg/kg, up to a maximum of 900 mg). Exposures (AUC) in children 2 to 11 years old with latent tuberculosis infection were higher (average 31%) than those observed in adults receiving rifapentine 900 mg once weekly (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
7.1.4 Geriatrics
Clinical studies with rifapentine did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. In a pharmacokinetic study with rifapentine, no substantial differences in the pharmacokinetics of rifapentine and 25-desacetyl metabolite were observed in the elderly compared to younger adults (see 10.3 Pharmacokinetics).
8 Adverse Reactions
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Rifapentine in combination with isoniazid given once weekly for 3 months (3RPT/INH) was compared to isoniazid given once daily for 9 months (9INH) in an open-label, randomized trial in patients with a positive tuberculin skin test, and at high risk for progression from latent tuberculosis infection to active tuberculosis disease. Rifapentine was dosed by weight, and isoniazid mg/kg dose was determined according to age (4.2 Recommended Dose and Dosage Adjustment) to a maximum of 900 mg each.
A total of 4040 patients received at least one dose of the 3RPT/INH regimen, including 348 children 2 to 17 years of age and 105 HIV -infected individuals. A total of 3759 received at least one dose of the 9INH regimen, including 342 children 2 to 17 years of age and 95 HIV-infected individuals.
Patients were followed for 33 months from the time of enrollment. Treatment-emergent adverse reactions were defined as those occurring during treatment and 60 days after the last dose of treatment. One hundred and sixty-one (4%) 3RPT/INH patients had a rifamycin hypersensitivity reaction, defined as either: a) one of the following: hypotension, urticaria, angioedema, acute bronchospasm, or conjunctivitis occurring in relation to study drug or b) at least four of the following symptoms occurring in relation to the study drug, with at least one symptom being CTCAE Grade 2 or higher: weakness, fatigue, nausea, vomiting, headache, fever, aches, sweats, dizziness, shortness of breath, flushing or chills. No specific definition was used for isoniazid hypersensitivity; 18 (0.5%) 9INH patients were classified as having a hypersensitivity reaction. Hepatotoxicity was defined as AST ≥3 × upper limit of normal in the presence of specific signs and symptoms of hepatitis, or AST >5 × upper limit of normal regardless of signs or symptoms. One hundred and thirteen (3%) 9INH patients and 24 (0.6%) 3RPT/INH patients developed hepatotoxicity.
One hundred and ninety-six patients (4.9%) in the 3RPT/INH arm discontinued treatment due to a treatment related adverse reaction and 142 patients (3.8%) in the 9INH arm discontinued treatment due to a treatment related adverse reaction. In the 3RPT/INH group, the most frequent treatment related adverse reaction resulting in treatment discontinuation was hypersensitivity reaction, occurring in 120 (3%) patients. In the 9INH group, the most frequent treatment related adverse reaction resulting in treatment discontinuation was hepatotoxicity, occurring in 76 (2%) patients.
Seventy-one deaths occurred, 31/4040, 0.77% in the 3RPT/INH group and 40/3759 (1.06%) in the 9INH group) during the 33-month study period. During the treatment emergent period, 11 deaths occurred, 4 in the 3RPT/INH group and 7 in the 9INH group. None of the reported deaths were considered related to treatment with study drugs or were attributed to tuberculosis disease. Table 3 presents select adverse reactions that occurred during the treatment emergent period in the main study in LTBI patients treated with 3RPT/INH or 9INH at a frequency greater than 0.5%.
Table 3: Select Adverse Reactions Occurring in 0.5% or Greater of Patients* in the Latent Tuberculosis Infection Main Study
System Organ Class Adverse Reaction | 3RPT/INH (N=4040) N (%) | 9INH (N=3759) N (%) |
|---|---|---|
| Immune system disorders | ||
| Hypersensitivity | 161 (4) | 18 (0.5) |
| Hepatobiliary disorders | ||
| Hepatitis | 24 (0.6) | 113 (3) |
| Nervous system disorders | ||
| Headache | 26 (0.6) | 17 (0.5) |
| Skin and subcutaneous tissue disorders | ||
| Skin reaction | 31 (0.8) | 21 (0.6) |
*Includes events reported through 60 days after last dose of study drug
HIV substudy
Two hundred HIV-infected patients with latent tuberculosis infection received at least one dose of study drugs in the main study and an additional 193 patients received at least one dose in the extension study (total of 393; 207 received 3RPT/INH and 186 received 9INH). Compared to the HIV-negative patients enrolled in the main study, a higher proportion of HIV-infected patients in each treatment arm experienced a treatment emergent adverse reaction, including a higher incidence of hepatotoxicity. Hepatotoxicity occurred in 3/207 (1.5%) patients in the 3RPT/INH arm and in 14/186 (7.5%) in the 9INH arm. Rifamycin hypersensitivity occurred in only one HIV-infected patient. Eleven deaths occurred during the 33-month follow up period (6/207 in the 3RPT/INH group and 5/186 in the 9INH group) including one death in the 9INH arm during the treatment emergent period. None of the reported deaths were considered related to treatment with study drugs or tuberculosis disease.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Six hundred and ninety children 2 to 17 years of age received at least one dose of study drugs in the main study. An additional 342 children 2 to 17 years of age received at least one dose in the pediatric extension study (total 1032 children; 539 received 3RPT/INH and 493 received 9INH).
No children in either treatment arm developed hepatotoxicity. Using the same definition for rifamycin hypersensitivity reaction as in the main study, 7 (1.3%) of children in the 3RPT/INH group experienced a rifamycin hypersensitivity reaction. Adverse reactions in children 2 to 11 years of age and 12 to 17 years of age were similar.
8.3 Less Common Clinical Trial Adverse Reactions
Blood and Lymphatic System Disorders: leukopenia, anemia, lymphadenopathy, neutropenia.
Eye Disorders: conjunctivitis.
Gastrointestinal Disorders: nausea, diarrhea, vomiting, abdominal pain, constipation, dry mouth, dyspepsia, esophageal irritation, gastritis, pancreatitis.
General Disorders and Administration Site Conditions: fatigue, pyrexia, asthenia, chest pain, chills, feeling jittery.
Infections and Infestations: pharyngitis, viral infection, vulvovaginal candidiasis.
Metabolism and Nutrition Disorders: hyperglycemia, gout, hyperkalemia, decreased appetite, hyperlipidemia.
Musculoskeletal and Connective Tissue Disorders: arthralgia, myalgia, back pain, rhabdomyolysis.
Nervous System Disorders: dizziness, convulsion, paresthesia, headache, neuropathy peripheral, syncope.
Psychiatric Disorders: depression, anxiety, disorientation, suicidal ideation.
Renal and Urinary Disorders: azotemia.
Reproductive System and Breast Disorders: vulvovaginal pruritus.
Respiratory, Thoracic and Mediastinal Disorders: cough, dyspnea, oropharyngeal pain, asthma, bronchial hyperactivity, epistaxis.
Skin and Subcutaneous Tissue Disorders: rash, hyperhidrosis, pruritus, urticaria.
8.5 Post-Market Adverse Reactions
- -marketing surveillance of rifapentine. Because these reactions are reported from a population of unknown size, it is not possible to estimate their frequency or establish a causal relationship to drug exposure.
Skin and subcutaneous tissue disorders: Severe cutaneous adverse reactions (SCARs) such as Stevens-Johnson syndrome (SJS) and drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome (see 7 Warnings and Precautions, Skin).
9 Drug Interactions
9.3 Drug-Behaviour Interactions
The interaction of rifapentine with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
Protease Inhibitors and Reverse Transcriptase Inhibitors
Rifapentine is an inducer of CYP450 enzymes. Concomitant use of RIFAPENTINE TABLETS with other drugs metabolized by these enzymes, such as protease inhibitors and certain reverse transcriptase inhibitors, may cause a significant decrease in plasma concentrations and loss of therapeutic effect of the protease inhibitor or reverse transcriptase inhibitor (see 7 Warnings and Precautions, Endocrine and Metabolism).
Fixed-Dose Combination of Efavirenz, Emtricitabine, and Tenofovir
Once-weekly coadministration of 900 mg rifapentine with the antiretroviral fixed-dose combination of efavirenz 600 mg, emtricitabine 200 mg and tenofovir disoproxil fumarate 300 mg in HIV-infected patients did not result in any substantial change in steady state exposures of efavirenz, emtricitabine, and tenofovir. No clinically significant change in CD4 cell counts or viral loads was noted.
Hormonal Contraceptives
RIFAPENTINE TABLETS may reduce the effectiveness of hormonal contraceptives. Patients using hormonal contraception should be advised to use an alternative non-hormonal contraceptive method or add a barrier method of contraception during treatment with RIFAPENTINE TABLETS (see 7 Warnings and Precautions, Reproductive Health, 7.1.1 Pregnancy, and 16 Non-Clinical Toxicology).
Cytochrome P450 3A4 and 2C8/9
Rifapentine is an inducer of cytochromes P450 3A4 and P450 2C8/9. Therefore, RIFAPENTINE TABLETS may increase the metabolism of other co-administered drugs that are metabolized by these enzymes. Induction of enzyme activities by rifapentine occurred within 4 days after the first dose. Enzyme activities returned to baseline levels 14 days after discontinuing rifapentine.
Rifampin has been reported to accelerate the metabolism and may reduce the activity of the following drugs; hence, RIFAPENTINE TABLETS may also increase the metabolism and decrease the activity of these drugs. Dosage adjustments of the drugs in Table 4 or of other drugs metabolized by cytochrome P450 3A4 or P450 2C8/9 may be necessary if they are given concurrently with RIFAPENTINE TABLETS.
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Drug – Drug Interaction with Isoniazid
Co-administration of rifapentine (900 mg single dose) and isoniazid (900 mg single dose), in fasted condition, did not result in any significant change in the exposure of rifapentine and isoniazid compared to when administered alone in fasted condition.
Rifapentine is an inducer of cytochrome P450 3A4 and 2C8/9. Therefore, it may increase the metabolism and decrease the activity of other co-administered drugs that are metabolized by these enzymes. Dosage adjustments of the co-administered drugs may be necessary if they are given concurrently with Rifapentine.
Drug – Drug Interaction with Indinavir
In a study in which 600 mg rifapentine was administered twice weekly for 14 days followed by rifapentine twice weekly plus 800 mg indinavir 3 times a day for an additional 14 days, indinavir Cmax decreased by 55% while AUC reduced by 70%. Clearance of indinavir increased by 3-fold in the presence of rifapentine while half-life did not change. But when indinavir was administered for 14 days followed by co-administration with rifapentine for an additional 14 days, indinavir did not affect the pharmacokinetics of rifapentine (see 7 Warnings and Precautions, Endocrine and Metabolism).
Table 4: Drug Interactions with RIFAPENTINE TABLETS: Dosage Adjustment May be Necessary
| Drug Class | Examples of Drugs Within Class |
|---|---|
| Antiarrhythmics | Disopyramide, mexiletine, quinidine, tocainide |
| Antibiotics | Chloramphenicol, clarithromycin, dapsone, doxycycline; |
| Fluoroquinolones (such as ciprofloxacin) | |
| Oral Anticoagulants | Warfarin |
| Anticonvulsants | Phenytoin |
| Antimalarials | Quinine |
| Azole Antifungals | Fluconazole, itraconazole, ketoconazole |
| Antipsychotics | Haloperidol |
| Barbiturates | Phenobarbital |
| Benzodiazepines | Diazepam |
| Beta-Blockers | Propranolol |
| Calcium Channel Blockers | Diltiazem, nifedipine, verapamil |
| Cardiac Glycoside Preparations | Digoxin |
| Corticosteroids | Prednisone |
| Fibrates | Clofibrate |
| Oral Hypoglycemics | Sulfonylureas (e.g., glyburide, glipizide) |
| Hormonal Contraceptives/Progestins | Ethinyl estradiol, levonorgestrel |
| Immunosuppressants | Cyclosporine, tacrolimus |
| Methylxanthines | Theophylline |
| Narcotic analgesics | Methadone |
| Phosphodiesterase-5 (PDE-5) Inhibitors | Sildenafil |
| Protease inhibitors and reverse transcriptase inhibitors | Indinavir, Fixed-dose combination of efavirenz, emtricitabine and tenofovir |
| Thyroid preparations | Levothyroxine |
| Tricyclic antidepressants | Amitriptyline, nortriptyline |
The conversion of rifapentine to 25-desacetyl rifapentine is mediated by an esterase enzyme. There is minimal potential for rifapentine metabolism to be inhibited or induced by another drug, based upon the characteristics of the esterase enzymes.
Since rifapentine is highly bound to albumin, drug displacement interactions may also occur (see 10.3 Pharmacokinetics).
9.5 Drug-Food Interactions
RIFAPENTINE TABLETS should be taken with meals. Administration of RIFAPENTINE TABLETS with a meal increases oral bioavailability and may reduce the incidence of gastrointestinal upset, nausea, and/or vomiting (see 4.4 Administration).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Therapeutic concentrations of rifampin have been shown to inhibit standard microbiological assays for serum folate and Vitamin B12. Similar drug-laboratory interactions should be considered for RIFAPENTINE TABLETS; thus, alternative assay methods should be considered.
10 Clinical Pharmacology
10.1 Mechanism of Action
Rifapentine, a cyclopentyl rifamycin, is an antimycobacterial agent. It inhibits DNA-dependent RNA polymerase in susceptible strains of Mycobacterium tuberculosis but does not affect mammalian cells at concentrations that are active against these bacteria (see 15 Microbiology).
10.3 Pharmacokinetics
When oral doses of rifapentine were administered once daily or once every 72 hours to healthy volunteers for 10 days, single dose AUC (0-∞) of rifapentine was similar to its steady-state AUCss (0-24h) or AUCss (0-72h) values, suggesting no significant auto-induction effect on steady-state pharmacokinetics of rifapentine. Steady-state conditions were achieved by day 10 following daily administration of rifapentine 600 mg. No plasma accumulation of rifapentine and 25-desacetyl rifapentine (active metabolite) is expected after once weekly administration of rifapentine.
The pharmacokinetic parameters of rifapentine and 25-desacetyl rifapentine on day 10 following oral administration of 600 mg rifapentine every 72 hours to healthy volunteers are described in Table 5.
Table 5: Pharmacokinetics of Rifapentine and 25-Desacetyl Rifapentine in Healthy Volunteers
| Parameter | Rifapentine | 25-desacetyl Rifapentine | |||||
|---|---|---|---|---|---|---|---|
| Mean ± SD (n=12) | |||||||
| Cmax (μg/mL) | 15.05 ± 4.62 | 6.26 ± 2.06 | |||||
| AUC (0-72h) (μg·h/mL) | 319.54 ± 91.52 | 215.88 ± 85.96 | |||||
| T1/2 (h) | 13.19 ± 1.38 | 13.35 ± 2.67 | |||||
| Tmax (h) | 4.83 ± 1.80 | 11.25 ± 2.73 | |||||
| Cl/F (L/h) | 2.03 ± 0.60 | -- | |||||
The pharmacokinetic parameters of rifapentine and 25-desacetyl rifapentine following single-dose oral administration of 900 mg rifapentine in combination with 900 mg isoniazid in fed conditions are described in Table 6.
Table 6: Mean ± SD Pharmacokinetic Parameters of Rifapentine and 25-Desacetyl Rifapentine in Healthy Volunteers When Rifapentine is Coadministered with Isoniazid Under Fed Conditions (N=16)
| Parameter | Rifapentine | 25-desacetyl Rifapentine |
|---|---|---|
| Cmax (μg/mL) | 25.8 ± 5.83 | 13.3 ± 4.83 |
| AUC (μg·h/mL) | 817 ± 128 | 601 ± 187 |
| T1/2(h) | 16.6 ± 5.02 | 17.5 ± 7.42 |
| Tmax (h)* | 8 (3-10) | 24 (10-36) |
| Cl/F (L/h) | 1.13 ± 0.174 | NA** |
* Median (Min-Max).
** Not Applicable.
Absorption
The absolute bioavailability of rifapentine has not been determined. The relative bioavailability (with an oral solution as a reference) of rifapentine after a single 600 mg dose to healthy adult volunteers was 70%. The maximum concentrations were achieved from 5 hours to 6 hours after administration of the 600 mg rifapentine dose.
The administration of rifapentine with a high fat meal increased rifapentine Cmax and AUC by 40% to 50% over that observed when rifapentine was administered under fasting conditions.
The administration of rifapentine (900 mg single dose) and isoniazid (900 mg single dose) with a low fat, high carbohydrate breakfast, led to a 47% and 51% increase in rifapentine Cmax and AUC, respectively. In contrast, the ingestion of the same meal decreased isoniazid Cmax and AUC by 46% and of 23%, respectively.
Distribution
In a population pharmacokinetic analysis in 351 tuberculosis patients who received 600 mg rifapentine in combination with isoniazid, pyrazinamide and ethambutol, the estimated apparent volume of distribution was 70.2 ± 9.1 L. In healthy volunteers, rifapentine and 25-desacetyl rifapentine were 97.7% and 93.2% bound to plasma proteins, respectively. Rifapentine was mainly bound to albumin. Similar extent of protein binding was observed in healthy volunteers, asymptomatic HIV-infected patients and hepatically impaired patients.
Metabolism/ Elimination
Following a single 600 mg oral dose of radiolabeled rifapentine to healthy volunteers (n=4), 87% of the total 14C-rifapentine was recovered in the urine (17%) and feces (70%). Greater than 80% of the total 14C-rifapentine dose was excreted from the body within 7 days. Rifapentine was hydrolyzed by an esterase enzyme to form a microbiologically active 25-desacetyl rifapentine. Rifapentine and 25-desacetyl rifapentine accounted for 99% of the total radioactivity in plasma. Plasma AUC(0-∞) and Cmax values of the 25-desacetyl rifapentine metabolite were one-half and one-third those of the rifapentine, respectively. Based upon relative in vitro activities and AUC(0-∞) values, rifapentine and 25-desacetyl rifapentine potentially contributes 62% and 38% to the clinical activities against M. tuberculosis, respectively.
Special Populations and Conditions
Pediatrics
In a pharmacokinetic study in pediatric patients (age 2 to 12 years), a single oral dose of 150 mg rifapentine was administered to those weighing less than 30 kg (n=11) and a single oral dose of 300 mg was administered to those weighing greater than 30 kg (n=12). The mean estimates of AUC and Cmax were approximately 30% to 50% lower in these pediatric patients than those observed in healthy adults administered single oral doses of 600 mg and 900 mg.
A study compared the pharmacokinetics of rifapentine in pediatric patients (age 2 years to 11 years) with latent tuberculosis infection (n=80) receiving rifapentine once weekly based on weight (15 mg/kg to 30 mg/kg, up to a maximum of 900 mg, see Table 1) to that of adults (n=77) receiving rifapentine 900 mg once weekly. Children who could not swallow whole tablets were administered crushed tablets mixed in soft food. Overall, the geometric mean AUC of rifapentine in this age group was 31% higher compared to adult patients receiving 900 mg rifapentine once weekly (720 versus 551 mcg h/mL). The geometric mean AUC of rifapentine was 60% higher in children administered whole tablets (884 versus 551 mcg h/mL) and 19% higher in children administered crushed tablets (656 versus 551 mcg·h/mL), as compared to exposures in adults. Pediatric patients administered crushed rifapentine had 26% lower rifapentine exposures compared to those pediatric patients who were given whole tablets.
Population pharmacokinetic analysis showed that rifapentine clearance adjusted to body weight decreased with increasing age of pediatric patients (2 to 18 years).
In another pharmacokinetics study of rifapentine in healthy adolescents (age 12 to 15 years), 600 mg rifapentine was administered to those weighing ≥45 kg (n=10) and 450 mg was administered to those weighing less than 45 kg (n=2). The pharmacokinetics of rifapentine was similar to those observed in healthy adults.
Geriatrics
Following oral administration of a single 600 mg dose of rifapentine to elderly (65 years and older) male healthy volunteers (n=14), the pharmacokinetics of rifapentine and 25-desacetyl metabolite were similar to that observed for young (18 to 45 years) healthy male volunteers (n=20).
Sex
In a population pharmacokinetics analysis of sparse blood samples obtained from 351 tuberculosis patients who received 600 mg rifapentine in combination with isoniazid, pyrazinamide and ethambutol, the estimated apparent oral clearance of rifapentine for males and females was 2.51 ± 0.14 L/h and 1.69 ± 0.41 L/h, respectively. The clinical significance of the difference in the estimated apparent oral clearance is not known.
Hepatic Insufficiency
Following oral administration of a single 600 mg dose of rifapentine to mild to severe hepatic impaired patients (n=15), the pharmacokinetics of rifapentine and 25-desacetyl metabolite were similar in patients with various degrees of hepatic impairment and to that observed in another study for healthy volunteers (n=12).
Renal Insufficiency
The pharmacokinetics of rifapentine has not been evaluated in renal impaired patients. Although only about 17% of an administered dose is excreted via the kidneys, the clinical significance of impaired renal function on the disposition of rifapentine and its 25-desacetyl metabolite is not known.
Asymptomatic HIV-Infected Volunteers
Following oral administration of a single 600 mg dose of rifapentine to asymptomatic HIV-infected volunteers (n=15) under fasting conditions, mean Cmax and AUC(0-∞) of rifapentine were lower (20%-32%) than that observed in other studies in healthy volunteers (n=55). In a cross-study comparison, mean Cmax and AUC values of the 25-desacetyl rifapentine, when compared to healthy volunteers were higher (6%-21%) in one study (n=20), but lower (15%-16%) in a different study (n=40). The clinical significance of this observation is not known. Food (850 total calories: 33 g protein, 55 g fat, and 58 g carbohydrate) increases the mean AUC and Cmax of rifapentine observed under fasting conditions in asymptomatic HIV-infected volunteers by about 51% and 53%, respectively.
11 Storage, Stability and Disposal
The product should be stored at 15 oC to 30 oC.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name: Rifapentine
Chemical name: 3-[N-(4-Cyclopentyl-1-piperazinyl) formimidoyl] Rifamycin
Molecular formula and molecular mass: C47H64N4O12, 877.03
Structural formula:
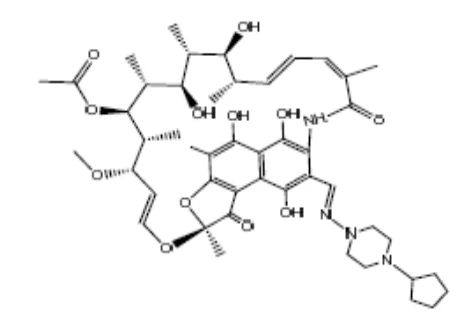
Physicochemical properties: Rifapentine is a light orange to dark red colored powder.
It is soluble in chloroform, slightly soluble in ethanol, acetone and ethyl acetate and practically insoluble in water at temperature 25°C ± 2°C.
14 Clinical Trials
14.1 Clinical Trials by Indication
Latent Tuberculosis Infection
A multicenter, prospective, open-label, randomized, active-controlled trial compared the effectiveness of 12 weekly doses of rifapentine in combination with isoniazid (3RPT/INH arm) administered by directly observed therapy to 9 months of self-administered daily isoniazid (9INH arm). The trial enrolled patients two years of age or older with positive tuberculin skin test and at high risk for progression to tuberculosis disease. Enrolled patients included those having close contact with a patient with active tuberculosis disease, recent (within two years) conversion to a positive tuberculin skin test, HIV-infection, or fibrosis on chest radiograph. Rifapentine was dosed by weight, for a maximum of 900 mg weekly. Isoniazid mg/kg dose was determined by age, for a maximum of 900 mg weekly in the 3RPT/INH arm and 300 mg daily in the 9INH arm (see 4.2 Recommended Dose and Dosage Adjustment). The outcome measure was the development of active tuberculosis disease, defined as culture confirmed tuberculosis in adults and culture-confirmed or clinical tuberculosis in children less than 18 years of age, at 33 months after trial enrollment. Patients who were found after enrollment to be ineligible because they had active tuberculosis disease, were contacts of a source case with culture-negative or drug-resistant tuberculosis disease cases or no information regarding susceptibility of M. tuberculosis, and young children lacking a positive TST on initial and repeat testing were excluded from the analysis. Active tuberculosis disease developed in 5 of 3074 randomized patients in the 3RPT/INH group (0.16%) versus 10 of 3074 patients in 9INH group (0.32%), for a difference in cumulative rates of 0.17%, 95% CI (-0.43, 0.09) (Table 7).
Table 7: Outcomes in Randomized Patients at 33 Months Post Enrollment*
* Similar results were observed when all enrolled patients were included in the analysis.
** Rate in the 3RPT/INH group minus the rate in the 9INH group.
The proportion of patients completing treatment was 81.2% in the 3RPT/INH group and 68.3% in the 9INH group for a difference (3RPT/INH-9INH) of 12.8% 95% CI (10.7, 15.0).
In the 9INH treatment group, two of the thirteen culture-confirmed cases were found to be isoniazid-monoresistant. In the 3RPT/INH treatment group, one of the seven cases was rifampin- resistant, isoniazid-susceptible M. bovis infection.
- Pediatric substudy
Enrollment of children was extended after the overall target number of patients was attained in the main study. Data from both the main study and the extension were pooled resulting in an eligible population for analysis of 375 children in the 3RPT/INH arm and 367 in the 9INH arm.
One child in the 9INH group developed tuberculosis (1/367, cumulative rate 0.32%) versus zero tuberculosis cases in the 3RPT/INH group (0/375) at 33 months post enrollment. The proportion of patients completing treatment in the 3RPT/INH and the 9INH groups was 87.5% and 79.6% respectively for a difference of 7.9%, 95% CI (2.5, 13.2).
- HIV substudy
Enrollment of HIV-positive patients was extended after the overall target number of patients was attained in the main study. Data from both the main study and the extension were pooled resulting in an eligible population for analysis of 206 patients in the 3RPT/INH group and 193 in the 9INH group. Tuberculosis disease developed in 2/206 patients in the 3RPT/INH group (cumulative rate, 1.01%) and in 6/193 patients in the 9INH group (cumulative rate, 3.45%). The proportion of patients completing treatment in the 3RPT/INH and 9INH groups was 88.8% and 63.7%, respectively for a difference of 25.1%, 95% CI (16.8, 32.9).
14.2 Comparative Bioavailability Studies
An open label, randomized, two-treatment, two-period, two-sequence, single-dose (150 mg dose as 1 x 150 mg), crossover, comparative oral bioavailability study of RIFAPENTINE TABLETS (Macleods Pharmaceuticals Ltd.) and PRIFTIN® (Sanofi-aventis U.S. LLC, USA) was conducted in 40 healthy, adult, human participants under fasting condition. Comparative bioavailability data from the 40 participants that were included in the statistical analysis are presented in the following table:
| Outcome | 3RPT/INH (n=3074) | 9INH (n=3074) | Difference**, 95% CI |
|---|---|---|---|
| Tuberculosis n (%) | 5 (0.16) | 10 (0.32) | -0.16 (-0.42, 0.01) |
| Cumulative TB Rate (%) | 0.17 | 0.35 | -0.17 (-0.43, 0.09) |
| Deaths | 22 (0.72) | 35 (1.14) | -0.42 (-0.91, 0.06) |
| Lost to Follow-Up | 320 (10.41) | 357 (11.61) | -1.20 (-2.77, -0.36) |
Table 8: Summary Table of the Comparative Bioavailability Data
Rifapentine (1 × 150 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 100164.87 107018.36 (32.81) | 95871.92 103795.98 (38.67) | 104.5 | 94.9 – 115.0 |
AUCI (ng·h/mL) | 104110.81 110586.13 (31.68) | 99562.92 107431.70 (37.83) | 104.6 | 95.5 – 114.5 |
CMAX (ng/mL) | 4780.89 5056.91 (30.81) | 4461.61 4715.63 (31.05) | 107.2 | 97.7 – 117.5 |
TMAX3 (h) | 4.33 (1.50 - 7.00) | 4.33 (1.50 - 7.00) | ||
T1/24 (h) | 12.83 (21.76) | 12.63 (20.05) | ||
1 RIFAPENTINE TABLETS, 150 mg (Macleods Pharmaceuticals Ltd.)
2 PRIFTIN® (rifapentine) tablets, 150 mg (Sanofi-aventis U.S. LLC, USA)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
An open label, randomized, two-treatment, two-period, two-sequence, single-dose (150 mg dose as 1 x 150 mg), crossover, comparative oral bioavailability study of RIFAPENTINE TABLETS (Macleods Pharmaceuticals Ltd.) and PRIFTIN® (Sanofi-aventis U.S. LLC, USA) was conducted in 24 healthy, adult, human participants under high-fat, high-calorie fed conditions condition. Comparative bioavailability data from the 21 participants that were included in the statistical analysis are presented in the following table:
Table 9: Summary Table of the Comparative Bioavailability Data
Rifapentine (1 × 150 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 125593.30 130942.40 (17.60) | 122914.30 128568.20 (20.76) | 102.2 | 98.6 – 106.0 |
AUCI (ng·h/mL) | 129038.37 134148.22 (17.18) | 126904.88 132261.68 (20.02) | 101.7 | 98.3 – 105.2 |
CMAX (ng/mL) | 5669.07 5813.83 (18.65) | 5598.02 5670.93 (14.72) | 101.3 | 93.5 – 109.6 |
TMAX3 (h) | 5.67 (5.00 - 18.00) | 5.67 (3.00 - 10.00) | ||
T1/24 (h) | 11.23 (15.60) | 11.77 (17.98) | ||
1 RIFAPENTINE TABLETS, 150 mg (Macleods Pharmaceuticals Ltd.)
2 PRIFTIN® (rifapentine) tablets, 150 mg (Sanofi-aventis U.S. LLC, USA)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 Microbiology
Mechanism of Action
Rifapentine, a cyclopentyl rifamycin, is an antimycobacterial agent. It inhibits DNA-dependent RNA polymerase in susceptible strains of Mycobacterium tuberculosis but does not affect mammalian cells at concentrations that are active against these bacteria. At therapeutic levels, rifapentine inhibits RNA transcription by preventing the initiation of RNA chain formation. It forms a stable complex with bacterial DNA-dependent RNA polymerase, leading to repression of RNA synthesis and cell death. Rifapentine and its 25-desacetyl metabolite accumulate in human monocyte-derived macrophages and are bactericidal to both intracellular and extracellular M. tuberculosis bacilli.
Rifapentine has a similar profile of microbiological activity to rifampin.
Mechanism of Resistance
The mechanism of resistance to rifapentine appears to be similar to that of rifampin. Bacterial resistance to rifapentine is caused by an alteration in the target site, the beta subunit of the DNA-dependent RNA polymerase, caused by a one-step mutation in the rpoB gene. The incidence of rifapentine resistant mutants in an otherwise susceptible population of M. tuberculosis strains is approximately one in 107 to 108 bacilli. Rifapentine resistance appears to be associated with monotherapy. Therefore, rifapentine should always be used in combination with other antituberculosis drugs.
Cross Resistance
M. tuberculosis organisms resistant to other rifamycins are likely to be resistant to rifapentine. A high level of cross-resistance between rifamycin and rifapentine has been demonstrated with M. tuberculosis strains. Cross-resistance between rifapentine and non-rifamycin antimycobacterial agents has not been identified in clinical isolates.
Susceptibility Test Methods
In vitro susceptibility tests should be performed according to published methods. Susceptibility test interpretive criteria and quality control ranges for in vitro susceptibility testing of rifapentine have not been established.
16 Non-Clinical Toxicology
Genotoxicity
Rifapentine was negative in the following genotoxicity tests: in vitro gene mutation assay in bacteria (Ames test); in vitro point mutation test in Aspergillus nidulans; in vitro gene conversion assay in Saccharomyces cerevisiae; host-mediated (mouse) gene conversion assay with Saccharomyces cerevisiae; in vitro Chinese hamster ovary cell/hypoxanthine-guanine phosphoribosyltransferase (CHO/HGPRT) forward mutation assay; in vitro chromosomal aberration assay utilizing rat lymphocytes; and in vivo mouse bone marrow micronucleus assay.
The 25-desacetyl metabolite of rifapentine was positive in the in vitro mammalian chromosome aberration test in V79 Chinese hamster cells but was negative in the in vitro gene mutation assay in bacteria (Ames test), the in vitro CHO/HGPRT forward mutation assay, and the in vivo mouse bone marrow micronucleus assay.
Carcinogenicity
Hepatocellular carcinomas were increased in male mice that were treated orally with rifapentine for two years at or above doses of 5 mg/kg/day (0.04 times a single human dose of 600 mg based on body surface area [BSA] conversion). In a two year rat study, there was an increase in nasal cavity adenomas in rats treated orally with rifapentine at 40 mg/kg/day (0.6 times a single human dose of 600 mg based on BSA conversion).
Reproductive and Developmental Toxicology
Fertility and reproductive performance were not affected by oral administration of rifapentine to male and female rats at doses of up to 20 mg/kg/day (0.3 times a single human dose of 600 mg based on BSA conversion).
Animal studies in rats and rabbits revealed embryofetal toxicity, including malformations and other adverse developmental outcomes, in both species. Pregnant rats given oral rifapentine during organogenesis (gestational day [GD] 5 through GD15) at 40 mg/kg/day (0.6 times a single human dose of 600 mg based on BSA comparisons) produced pups with cleft palates and mal-positioned aortic arches, delayed ossification, increased number of ribs, a decrease in litter size and mean litter weight, an increase in number of stillbirths, and an increase in mortality during lactation.
When rifapentine was administered orally to mated female rats late in gestation, at 20 mg/kg/day (0.3 times a single human dose of 600 mg based on BSA), pup weights and gestational survival (live pups born/pups born) were reduced compared to controls. Increased resorptions and post-implantation loss, decreased mean fetal weights, increased numbers of stillborn pups, and slightly increased pup mortality during lactation were also noted.
When pregnant rabbits received oral rifapentine at 10 mg/kg to 40 mg/kg (0.3 times to 1.3 times a single human dose of 600 mg based on BSA) during organogenesis (GD6 to GD18), major fetal malformations occurred including: ovarian agenesis, pes varus, arhinia, microphthalmia, and irregularities of the ossified facial tissues. At 40 mg/kg/day, there were increases in post-implantation loss and the incidence of stillborn pups.