


Product Monograph - Salofalk (Abbvie, 500 mg, 1000 mg)
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Renal | 06/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Skin | 06/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.2 Breast Feeding | 11/2021 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 4
4.4 Administration ......................................................................................................... 4
4.5 Missed Dose ............................................................................................................. 5
5 OVERDOSAGE ............................................................................................................ 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 5
7 WARNINGS AND PRECAUTIONS ................................................................................. 5
7.1 Special Populations .................................................................................................. 7
7.1.1 Pregnant Women ............................................................................................... 7
7.1.2 Breast-feeding .................................................................................................... 8
7.1.3 Pediatrics ............................................................................................................ 8
7.1.4 Geriatrics ............................................................................................................ 8
8 ADVERSE REACTIONS................................................................................................. 8
8.1 Adverse Reaction Overview ..................................................................................... 8
8.2 Clinical Trial Adverse Reactions ............................................................................... 8
8.5 Post-Market Adverse Reactions ............................................................................. 10
9 DRUG INTERACTIONS .............................................................................................. 11
9.2 Drug Interactions Overview ................................................................................... 11
9.4 Drug-Drug Interactions .......................................................................................... 11
9.5 Drug-Food Interactions .......................................................................................... 11
9.6 Drug-Herb Interactions .......................................................................................... 11
9.7 Drug-Laboratory Test Interactions......................................................................... 11
10 CLINICAL PHARMACOLOGY ...................................................................................... 11
10.1 Mechanism of Action ....................................................................................... 11
10.2 Pharmacodynamics .......................................................................................... 12
10.3 Pharmacokinetics ............................................................................................. 13
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 13
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 13
PART II: SCIENTIFIC INFORMATION ..................................................................................... 14
13 PHARMACEUTICAL INFORMATION .......................................................................... 14
14 CLINICAL TRIALS ...................................................................................................... 14
14.1 Clinical Trials by Indication .............................................................................. 14
Ulcerative proctitis ........................................................................................................... 14
15 MICROBIOLOGY ...................................................................................................... 15
16 NON-CLINICAL TOXICOLOGY .................................................................................... 15
PATIENT MEDICATION INFORMATION ................................................................................ 18
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
SALOFALK® (mesalamine suppositories) is indicated for:
- management of ulcerative proctitis.
- as adjunctive therapy in more extensive distal ulcerative colitis (DUC).
1.1 Pediatrics
Information on the safety and efficacy of SALOFALK in children is limited. Therefore, use should be limited to situations where a clear benefit is expected. SALOFALK should not be used in infants under two years of age.
1.2 Geriatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2 CONTRAINDICATIONS
SALOFALK is contraindicated in:
- patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- patients with severe renal impairment (GFR<30ml/min/1.73m2) and/or severe hepatic impairment. See 7 WARNINGS AND PRECAUTIONS.
- cases of existing gastric or duodenal ulcer.
- patients with urinary tract obstructions.
- patients hypersensitive to salicylates, including acetylsalicylic acid (e.g. Aspirin®), may also be hypersensitive to this medication.
4 DOSAGE AND ADMINISTRATION
4.2 Recommended Dose and Dosage Adjustment
- One 500 mg SALOFALK rectal suppository is self-administered on a twice a day or three times a day basis. One 1000 mg SALOFALK rectal suppository is self-administered on a once daily basis, at bedtime. The usual adult dose is 1.0 - 1.5 g/day and dosing is continued until a significant response is achieved or until the patient achieves remission. Dose tapering is recommended. Abrupt discontinuation is not recommended. Best results are expected with prolonged retention.
Health Canada has not authorized an indication for pediatric use. See 1.1 Pediatrics.
4.4 Administration
For rectal use only. SALOFALK suppositories are self-administered, one 500 mg suppository 2 or 3 times/day, and one 1000 mg suppository 1 time daily at bedtime. The suppository should be retained for 1 to 3 hours or longer to achieve the maximum benefit. While the effect of the suppositories may be seen within 3 to 21 days, the usual course of therapy would be from 3 to 6 weeks depending on symptoms and sigmoidoscopic findings.
Patient Instructions:
- I. Detach one suppository from the strip of suppositories.
- II. Hold suppository upright and carefully remove the plastic wrapper.
- III. Avoid excessive handling of suppository, which is designed to melt at body temperature.
- IV. Insert suppository completely into rectum with gentle pressure, pointed end first.
- V. A small amount of lubricating gel may be used on the tip of the suppository to assist insertion.
In children, information on the safety and efficacy of mesalamine suppositories is limited. Therefore, use should be limited to situations where a clear benefit is expected.
4.5 Missed Dose
If a dose of SALOFALK is missed, it should be used as soon as possible, unless it is almost time for the next dose. A patient should not use two doses at the same time to make up for a missed dose.
5 OVERDOSAGE
There has been no clinical experience with mesalamine overdosage. However, because mesalamine is an aminosalicylate, the symptoms of overdose may mimic the symptoms of salicylate overdose; therefore, measures used to treat salicylate overdose may be applied to mesalamine overdose. Under ordinary circumstances, local mesalamine absorption from the colon is limited. There is no specific antidote and treatment is symptomatic and supportive.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 Dosage Forms, Strengths, Composition and Packaging
SALOFALK is gluten-free and phthalate-free.
Each smooth light tan to grey, bullet-shaped suppository is available in strips of 6, boxes of 30 suppositories.
7 WARNINGS AND PRECAUTIONS
General
SALOFALK should be used only if the benefits clearly outweigh the risks in patients with underlying, bleeding or clotting disorders as well as during pregnancy and lactation.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Rectal | suppositories 500mg, 1000 mg | Witepsol H-15 (suppository wax base). |
Patients with renal dysfunction, or elevated Blood Urea Nitrogen (BUN), or elevated serum creatinine, or with proteinuria, should be carefully monitored while receiving SALOFALK.
Concomitant treatment with mesalamine can increase the risk of myelosuppression in patients receiving azathioprine or 6-mercaptopurine.
Acute Intolerance Syndrome
Mesalamine has been implicated in the production of an acute intolerance syndrome characterized by cramping, acute abdominal pain and bloody diarrhoea, sometimes fever, headache and a rash; in such cases prompt withdrawal is required. The patient’s history of sulfasalazine intolerance, if any, should be re-evaluated. If a rechallenge is performed later in order to validate the hypersensitivity, it should be carried out under close supervision and only if clearly needed, giving consideration to reduced dosage. The possibility of increased absorption of mesalamine and concomitant renal tubular damage as noted in the preclinical studies must be kept in mind. Patients on concurrent mesalamine products which contain or release mesalamine and those with pre-existing renal disease should be carefully monitored with urinalysis, and BUN and creatinine testing.
Carcinogenesis and Mutagenesis
Carcinogenicity studies in animals and mutagenicity tests were negative. See 16 NON-CLINICAL TOXICOLOGY.
Cardiovascular
Cardiac side effects, including pericarditis and myocarditis have been uncommonly reported with the use of mesalamine.
Cases of pericarditis have also been reported as manifestations of inflammatory bowel disease. Discontinuation of mesalamine may be warranted in some cases, but rechallenge with mesalamine can be performed under careful clinical observation should the continued therapeutic need for mesalamine be present.
Driving and Operating Machinery
There are no data available on the effects of mesalamine on ability to drive and use machines.
Gastrointestinal
Epigastric pain, also commonly associated with inflammatory bowel disease and prednisone or sulfasalazine (SAS) therapy (18%), should be investigated in order to exclude pericarditis and pancreatitis either as adverse drug reactions to mesalamine or secondary manifestations of inflammatory bowel disease.
Hepatic/Biliary/Pancreatic
There have been reports of hepatic failure and increased liver enzymes in patients with pre-existing liver disease when treated with 5-Amino salicylic acid (5-ASA)/Mesalazine products. Therefore, SALOFALK is contraindicated in patients with severe hepatic impairment. See 2 CONTRAINDCATIONS. In patients with mild to moderate liver function impairment, caution should be exercised and SALOFALK should only be used if the expected benefit clearly outweighs the risks to the patients.
Renal
Reports of renal impairment, including minimal change nephropathy, and acute or chronic interstitial nephritis have been associated with mesalamine products and pro-drugs of mesalamine. SALOFALK is contraindicated in patients with severe renal impairment. See 2 CONTRAINDICATIONS. In patients with mild to moderate renal dysfunction history of renal disease or using concomitant nephrotoxic drugs, caution should be exercised and SALOFALK should be used only if the benefits outweigh the risks.
Cases of nephrolithiasis have been reported with the use of mesalazine, including stones with a 100% mesalazine content. It is recommended to ensure adequate fluid intake during treatment.
Patients on mesalamine, especially those with pre-existing renal disease, should be carefully monitored with urinalysis, and BUN and creatinine testing. Initial assessment and periodic monitoring of the renal function is recommended since mesalamine is substantially excreted by the kidney, and prolonged mesalamine therapy may damage the kidneys. Discontinue SALOFALK if renal function deteriorates while on therapy.
Because elderly patients are more likely to have decreased renal function, closer monitoring of the renal function may be needed.
Sensitivity/Resistance
Caution should be exercised when mesalamine (5-ASA) is initially used in patients known to be allergic to sulfasalazine. These patients should be instructed to discontinue therapy if sign of rash or pyrexia become apparent. In case of an allergic reaction, appropriate measures (standard of care) should be taken.
Skin
Severe Cutaneous Reactions:
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) and toxic epidermal necrolysis (TEN), have been reported in association with mesalamine treatment. Mesalamine should be discontinued at the first appearance of signs and symptoms of severe skin reactions, such as skin rash, mucosal lesions, or any other sign of hypersensitivity.
Photosensitivity:
Patients treated with mesalamine or sulfasalazine who have pre-existing skin conditions such as atopic dermatitis and atopic eczema have reported more severe photosensitivity reactions. Advise patients to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors.
7.1 Special Populations
7.1.1 Pregnant Women
SALOFALK should be used during pregnancy only if the benefits clearly outweigh the risks to the foetus. 5-ASA is known to cross the placental barrier, and no clinical studies have been performed in pregnant women.
Animal studies did not show evidence of impaired fertility or harm to the foetus due to mesalamine see 16 NON-CLINICAL TOXICOLOGY, however, because animal reproduction studies are not always predictive of human response, SALOFALK should be used during pregnancy only if clearly needed.
7.1.2 Breast-feeding
There are no clinical trial studies in nursing women. SALOFALK should be used in nursing women only if the benefits to the mother clearly outweigh the risks to the child. Mesalamine and its main metabolite N-acetyl-5-ASA are excreted in breast milk. The concentration of mesalamine is much lower than in maternal blood, but the metabolite N-acetyl-5-ASA appears in similar concentrations.
When mesalamine is used in nursing women, infants should be monitored for changes in stool consistency. If the infant develops diarrhoea breast-feeding should be discontinued. Cases of diarrhoea in breastfed infants exposed to mesalamine have been reported.
Isolated weight decrease in nursing infant has been reported during post-marketing experience with mesalamine.
7.1.3 Pediatrics
Pediatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Clinical studies of mesalamine did not include sufficient number of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Mesalamine is substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, it may be useful to monitor renal function.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Hypersensitivity reactions have been reported in a sub-group of patients known to be allergic to sulfasalazine including rash, pyrexia, and dizziness with reactions occurring at the onset of therapy and resolving promptly following discontinuation.
Other manifestations of hypersensitivity reported with mesalamine include acute pancreatitis, hepatitis, pericarditis, interstitial nephritis, interstitial pneumonia and pleural effusion. Interstitial pneumonia, pancreatitis and pericarditis have also been reported as manifestations of inflammatory bowel disease.
As with all 5-ASA products, exacerbations of ulcerative colitis characterized by cramping acute abdominal pain and diarrhoea have been reported with mesalamine.
Other reported side effects include headache, flatulence, nausea, and hair loss, but do not appear to be common. Retreatment is not always associated with repeated hair loss. Aplastic anaemia has been reported in the literature with unspecified formulations of mesalamine.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Table 2 Clinical Trial Adverse Events Reported in > 0.1% of Patients
SALOFALK N=841 % | Placebo N=176 % | |
Cardiac Disorders Pericarditis | 0.1 | 0.0 |
Gastrointestinal Disorders Abdominal pain Flatulence Nausea Diarrhoea Abdominal distension Haemorrhoids Proctalgia Constipation Anorectal discomfort Pancreatitis Condition aggravated | 7.9 6.0 5.6 2.1 1.4 1.3 1.1 0.9 0.5 0.1 0.1 | 7.9 4.5 6.8 3.9 1.1 0.0 0.0 2.2 1.7 0.0 0.0 |
General Disorders and Administration Site Conditions Fatigue Pyrexia Administration site reaction Oedema peripheral Asthenia | 3.3 3.0 1.3 0.5 0.1 | 4.5 0.0 0.5 6.2 2.2 |
Infections and Infestations Influenza Urinary tract infection Upper respiratory tract infection | 5.2 0.5 0.1 | 0.5 2.2 0.5 |
Musculoskeletal, and Connective Tissue Disorders Arthralgia Back pain | 2.0 1.3 | 1.1 0.5 |
SALOFALK N=841 % | Placebo N=176 % | |
Nervous System Disorders Headache Dizziness Insomnia | 6.7 1.7 0.1 | 11.3 2.8 1.7 |
Respiratory, Thoracic and Mediastinal Disorders Pharyngolaryngeal pain | 2.0 | 2.8 |
Skin and Subcutaneous Tissue Disorders Rash Spots Pruritus Alopecia | 2.8 2.2 1.1 0.8 | 2.2 5.1 0.5 1.1 |
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during the post-approval use of SALOFALK. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: Agranulocytosis
Cardiac Disorders: Myocarditis, Pericarditis
Eye Disorders: Eye swelling
Gastrointestinal Disorders: Abdominal pain (upper, lower), Abdominal cramps, Abdominal distension, Abnormal faeces, Anal pruritus, Anorectal discomfort, Constipation, Diarrhoea, Faeces discoloured, Flatulence, Frequent bowel movements, Mucus stools, Nausea, Painful defecation, Pancreatitis, Proctalgia, Rectal discharge, Rectal tenesmus, Stomach discomfort, Vomiting
General Disorders and Administration Site Conditions: Fatigue, Medication residue, Pain, Pyrexia, Mesalamine-induced acute intolerance syndrome
Immune System Disorder: Anaphylactic reaction
Hepatobiliary Disorders: Hepatic impairment, including hepatic failure or hepatitis
Nervous System Disorders: Burning sensation, Dizziness, Headache, Intracranial hypertension
Renal and Urinary Disorders: Nephrolithiasis
Respiratory, Thoracic and Mediastinal Disorders: Allergic and fibrotic lung reactions Dyspnoea, Eosinophilic pneumonia, Interstitial alveolitis, Pleurisy
Skin And Subcutaneous Tissue Disorder: Alopecia, Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), Erythema, Photosensitivity, Pruritus, Rash, Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN), Urticaria
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Interaction between azathioprine, 6-mercaptopurine and aminosalicylates (including mesalamine) can increase the risk of leucopenia. Other potential interactions with a number of drugs could occur. See 9.4 Drug-Drug Interactions.
9.4 Drug-Drug Interactions
Interaction between azathioprine, 6-mercaptopurine and aminosalicylates including mesalamine, has been reported with oral mesalamine. Concomitant treatment with mesalamine can increase the risk of myelosuppression in patients receiving azathioprine or 6-mercaptopurine. An increase in whole blood 6-thioguanine nucleotide (6-TGN) concentrations has been reported although the mechanism of this interaction remains unclear.
Mesalamine could also increase renal and hematologic toxicity of methotrexate by additive effect and diminished absorption of folic acid.
The hypoglycemic effect of sulfonylureas may be enhanced. Interactions with coumarin, methotrexate, probenecid, sulfinpyrazone, spironolactone, furosemide and rifampicin cannot be excluded. Potentiation of undesirable glucocorticoid effects on the stomach is possible.
A theoretical interaction of salicylates with Varicella Virus Vaccine (chicken pox vaccine) might increase the risk of Reye’s syndrome; as a result, the use of salicylates (including mesalamine) is discouraged for six weeks following Varicella vaccination.
The concurrent use of mesalamine with known nephrotoxic agents, including nonsteroidal anti-inflammatory drugs (NSAIDs) may increase the risk of nephrotoxicity. Monitor patients using nephrotoxic drugs for changes in renal function and mesalamine-related adverse reactions.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Several reports of possible interference with measurements, by liquid chromatography, of urinary normetanephrine causing a false-positive test result have been observed in patients exposed to sulfasalazine or its metabolite, mesalamine/mesalazine.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The mechanism of action of mesalamine (5-aminosalisylic acid, 5-ASA), is not fully understood, but appears to be topical rather than systemic. Inflammatory intestinal disease is often accompanied by diffuse tissue reactions including ulceration and cellular infiltration of lymphocytes, plasma cells, eosinophils, polymorphonuclear cells and activated phagocytic cells.
The interference of mesalamine with either leukotriene or prostaglandin metabolism may play a major role in suppressing the inflammatory response mechanism. 5-ASA prevents accumulation of thromboxane B2 and 6-keto-prostaglandin F1. Both 5-ASA and SAS reverse H2O, and Cl-secretion and increase Na+ secretion in experimentally-induced colitis in guinea pigs. SAS and 5-ASA are known to inhibit polymorphonuclear cell migration possibly via lipoxygenase inhibition at concentrations lower than those required to inhibit prostaglandin synthesis. It is thus possible that both SAS and 5-ASA are capable of inhibiting both pathways via lipoxygenase inhibition.
Intestinal secretion is stimulated not only by prostaglandins but also by the metabolites of arachidonic acid generated via the lipoxygenase pathway. Upon phagocytic activation and arachidonic acid metabolism activation, reactive oxygen metabolites are generated. 5-ASA acts as a dose dependent antioxidant which scavenges oxygen derived free radicals produced by activated phagocytes. In addition, 5-ASA associates with the membrane surface, allowing chain breaking anti-oxidant activity when peroxidation is initiated within the membrane. 5-ASA is able to block initiation of oxidation from solution as well as propagation within the membrane. 5-ASA also inhibits the formation of both eicosanoids and cytokines.
10.2 Pharmacodynamics
SALOFALK contains mesalamine 5-aminosalisylic acid (5-ASA), the active principle of the prodrug sulfasalazine. Although the 5-ASA mode of action is not clear, it appears to be multi-factorial. 5-ASA is thought to affect the inflammatory process through its ability to inhibit prostaglandin synthesis, interfere with leukotriene synthesis and consequent leukocyte migration as well as act as a potent scavenger of free radicals. Regardless of the mode of action, 5-ASA appears to be active mainly topically rather than systemically. Rectal administration as 500 or 1000 mg suppositories of mesalamine (5-aminosalicylic acid) allows for direct targeting of free 5-ASA to the sites of inflammation along the mucosal lumen of the rectum, sigmoid and distal large bowel.
Animal Studies
5-ASA (mesalamine) is the active moiety of the prodrug sulfasalazine which acts to suppress inflammatory bowel disease. Animal pharmacology tests were conducted on 5-ASA using the oral route of administration for most tests, at a dose of 500 mg/kg in order to simulate practice relevant conditions. No adverse effect of 5-ASA on the following parameters or in the following animal pharmacology tests could be established: tremorine antagonism, hexobarbital sleep time, motor activity, anticonvulsant action (metrazol and electric shock), blood pressure, heart rate, respiratory rate (up to 10 mg/kg, i.v.), tocolysis (antispasmodic assay), local anaesthesia, antihyperthermal and antipyretic effects. In the paw-edema test with carrageen injection, 200 mg/kg per os proved ineffective, but 500 mg/kg 5-ASA per os exhibited mild antiphlogistic action.
In the animal renal function tests (natriuresis and diuresis), no biologically relevant effects of 200 mg/kg per os were demonstrated. After 600 mg/kg, marked functional changes were observed: increases in total urinary output, natriuresis and proteinuria. The urinary sediment contained an increased number of erythrocytes and epithelial cells. Both potassium elimination and specify weight were reduced. It can be concluded from these experiments that even high doses of 5-ASA have no effect on vital parameters. Disturbances in renal function are to be expected only at dosages equivalent to a single dose at least 8 to 10 times the daily dose in man.
10.3 Pharmacokinetics
Absorption
Mesalamine (5-ASA) administered as a rectal suppository is variably absorbed. Systemic absorption of rectally administered 5-ASA is low as shown by urinary recoveries which range from 5% to 35% of the daily dose administered. In patients with ulcerative colitis treated with mesalamine 500 mg rectal suppositories, administered once every eight hours for six days, the mean mesalamine peak plasma concentration (Cmax) was 353 ng/mL (CV=55%) following the initial dose and 361 ng/mL (CV=67%) at steady state. The mean minimum steady state plasma concentration (Cmin) was 89 ng/mL (CV=89%). Absorbed mesalamine does not accumulate in the plasma.
Distribution:
Mesalamine administered as rectal suppositories distributes in rectal tissue to some extent. In patients with ulcerative proctitis treated with mesalamine 1000 mg rectal suppositories, rectal tissue concentrations for 5-ASA and N-acetyl-5-ASA have not been rigorously quantified.
Metabolism:
Mesalamine is extensively metabolized by acetylation. The only major metabolite of 5-ASA identified in man is N-acetyl-5-aminosalicylic acid (N-Ac-5-ASA). The site of metabolism has not been elucidated. In patients with ulcerative colitis treated with one 500 mg mesalamine rectal suppository every eight hours for 6 days, peak concentrations (Cmax) of N-acetyl-5-ASA ranged from 467 ng/mL to 1399 ng/mL following the initial dose and from 193 ng/mL to 1304 ng/mL at steady state.
The influence of renal and hepatic impairment on pharmacokinetics of mesalamine has not been evaluated.
Elimination
Mesalamine is eliminated from plasma mainly by urinary excretion, predominantly as N-acetyl-5-ASA. In patients with ulcerative proctitis treated with one mesalamine 500 mg rectal suppository every eight hours for six days, ≤ 12% of the dose was eliminated in urine as unchanged 5-ASA and 8-77% as N-acetyl-5-ASA following the initial dose. At steady state, ≤ 11% of the dose was eliminated as unchanged 5-ASA and 3-35% as N-acetyl-5-ASA. The mean elimination half-life was five hours (CV=73%) for 5-ASA and six hours (CV=63%) for N-acetyl-5-ASA following the initial dose. At steady state, the mean elimination half-life was seven hours for both 5-ASA and N-acetyl-5-ASA (CV=102% for 5-ASA and 82% for N-acetyl-5-ASA).
11 STORAGE, STABILITY AND DISPOSAL
SALOFALK must be stored below 25°C. Can be refrigerated. Keep away from direct heat, light and humidity.
Disposal of SALOFALK should be in keeping with recommendations governing the disposal of pharmaceutical waste.
12 SPECIAL HANDLING INSTRUCTIONS
Avoid excessive handling of suppository, which is designed to melt at body temperature. SALOFALK will cause staining of direct contact surfaces, including but not limited to fabrics, flooring, painted surfaces, marble, granite, vinyl, and enamel.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: 5-aminosalicylic acid, mesalamine
Chemical name: 5-aminosalicylic acid (5-ASA)
Molecular formula and molecular mass: C7H7NO3 153.14
Structural formula:
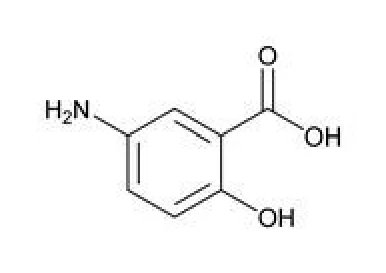
Physicochemical properties:
Description: 5-aminosalicylic acid is a light tan to pink, needle shaped, crystalline powder.
Solubility: Slightly soluble in water, very slightly soluble in methanol and practically insoluble in chloroform; soluble in diluted HCl and diluted alkali hydroxides.
Melting Range: 272°-280°C
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Ulcerative proctitis
Table 3 Summary of patient demographics for clinical trials in active proctitis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (years) | Sex | ||
| Study 1 | double-blind, placebo-controlled multicenter study | 500 mg mesalamine three times daily (1.5 g/day) Rectal suppository 6 weeks | n = 39 | 39 (17 to 73) | 34 M / 45 F | ||
| placebo | n = 40 | ||||||
A double-blind, placebo-controlled multicenter study was conducted in North America in patients with mild to moderate active proctitis. The primary measures of efficacy were clinical disease activity index
[DAI], sigmoidoscopic and histological evaluations. The dosage regimen: was 500 mg mesalamine three times daily (1.5 g/day). A total of 79 patients were studied (39 patients received mesalamine suppositories, and 40 patients received placebo). Patients were evaluated clinically and sigmoidoscopically after three and six weeks of suppository treatment. Patients were 17 to 73 years of age (mean = 39 years), 57% were female, and 97% were white. Patients had an average extent of proctitis (upper disease boundary) of 10.8 cm and 84% of patients had multiple prior episodes of proctitis.
Study Results
Study 1: Compared to placebo, mesalamine suppository treatment was statistically (p < 0.01) superior with respect to improvement in stool frequency, rectal bleeding, mucosal appearance, and disease severity. Mesalamine-treated patients had an 80.4% mean reduction in DAI (p < 0.05) compared to placebo (36.8%) and 84.4% of mesalamine patients were considered ‘much improved’ by the investigator (p < 0.01) at 6 weeks. Daily diary records revealed a significant improvement in rectal bleeding in the mesalamine-treated patients (p < 0.05) within the first week compared to placebo indicating a faster onset of action. The effectiveness of mesalamine suppositories was statistically significant irrespective of sex, extent of proctitis, duration of current episode or duration of disease.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Animal studies to date show the kidney to be the only significant target organ for 5-ASA toxicity in rats and dogs. At high doses, the lesions produced consisted of papillary necrosis and multifocal proximal tubular injury. In rats, the no-effect levels were 160 mg/kg/day for females and 40 mg/kg/day for males (minimal and reversible tubular lesions seen) after 13 weeks of oral administration. In dogs, the no-effect level in both males and females was 40 mg/kg/day after 6 months of oral administration. In this six-month oral toxicity study in dogs, doses of 80 mg/kg/day (about 1.4 times the recommended human intra-rectal dose, based on body surface area) and higher, caused renal pathology similar to that described for the rat. In a rectal toxicity study of mesalamine suppositories in dogs, a dose of 166.6 mg/kg (about 3.0 times the recommended human intra-rectal dose, based on body surface area) produced chronic nephritis and pyelitis. Aside from gastric lesions, heart lesions and bone marrow depression seen in some of the rats at the 640 mg/kg level and considered secondary effects of kidney damage, no other signs of systemic toxicity were noted at daily doses up to 160 mg/kg in rats and 120 mg/kg in dogs for 13 weeks and six months, respectively.
In the 12-month oral toxicity study in dogs, keratoconjunctivitis sicca (KCS) occurred at oral doses of 40 mg/kg/day (about 0.72 times the recommended human intra-rectal dose, based on body surface area) and above.
Carcinogenicity: Administration of doses of 0, 50, 100 and 320 mg/kg/day for 127 weeks in rats did not result in significant differences in unscheduled deaths, clinical signs, nodules or masses, between groups. Ophthalmoscopic investigations revealed no treatment-related changes. Treatment with SALOFALK was not associated with oncogenic changes or an increased tumor risk. The assessment of hematology, clinical biochemistry and urinalysis indicated no changes of toxicological significance at 13, 26 and 52 weeks of treatment.
After 127 weeks, analysis of the lesions indicated slight substance-related and dose-dependent toxic changes as degenerative kidney damage and hyalinization of tubular basement membrane and Bowman’s capsule in the 100 mg and 320 mg/kg/day groups. Ulceration of the gastric mucosa and atrophy of the seminal vesicles were also more frequent in the 320 mg/kg/day group.
Genotoxicity: 5-ASA was not mutagenic in the Ames test, E. coli reverse mutation assay, mouse micronucleus test, sister chromatid exchange assay, or in a chromosomal aberrations assay. In contrast, sulfapyridine, which is the other primary metabolite of salicylazosulfapyridine, has tested positive in certain mutagenicity tests.
Reproductive and Developmental Toxicology: Teratology studies with 5-ASA have been performed in rats at oral doses up to 320 mg/kg/day and in rabbits at oral doses up to 495 mg/kg/day (about 1.7 and 5.4 times the recommended human intra-rectal dose, respectively). The battery of tests completed to date has shown that 5-ASA is devoid of embryotoxicity and teratogenicity in rats and rabbits; that it does not affect male rat fertility after five weeks of oral administration at 296 mg/kg/day; and that it lacks the potential to affect late pregnancy, delivery, lactation or pup development in rats.
Other Studies
Nephrotoxic potential of 5-aminosalicylic acid: Owing to its structural relationship to phenacetin, the aminophenols and salicylates, 5-ASA was included in a series of compounds studied following identification of antipyretic-analgesic nephropathy in humans. Calder et al. has reported in rats that in addition to the proximal tubule necrosis seen with acetylsalicylic acid (e.g. Aspirin®) and phenacetin derivatives, 5-ASA produced papillary necrosis, following single intravenous doses ranging from 150 mg/kg to 872 mg/kg.
Diener et al. have shown that oral doses of 5-ASA of 30 mg/kg and 200 mg/kg daily for four weeks failed to produce any adverse effects on kidney function or histology in rat.
In a 13-week rat study, there were no renal lesions after four weeks in the animals receiving up to 160 mg/kg orally per day, but severe papillary necrosis and proximal tubular injury were seen in most animals receiving 640 mg/kg orally per day. At 13 weeks, the female animals were free of pathology up to 160 mg/kg; minimal and reversible lesions in the tubules occurred in a few males (with no changes in renal function) at the 40 mg/kg/day level. After six months of oral administration in dogs, no toxicity was seen in the 40 mg/kg/day group. At 80 mg/kg/day, two of eight treated dogs showed slight to moderate renal papillary necrosis. These dogs as well as two others showed minimal to moderate tubular lesions. At 120 mg/kg/day, two females had slight papillary necrosis. These and two others showed minimal to moderate tubule injury.
5-ASA rectal irritation challenge in dogs: A rectal mucosa irritation study was designed and conducted to determine if 5-ASA rectal suspension causes any mucosal tissue stress either histologically or macroscopically. The test was carried out blind against placebo, administering one rectal suspension per day.
Treated dogs (n = 10) received 2.0 g of 5-ASA which was retained for an average of 5.5 hours over the 27-day study. The placebo group (n = 6) received suspensions of the same vehicle composition, but without 5-ASA. Calcium carbonate and food colouring were used in place of 5-ASA to mimic its appearance in the suspension formula. The rectal suspension control group (n = 2) received physiological saline enemas of equivalent volume daily. Seven days prior to dosing and after Days 15 and 30, all animals were given a proctologic examination with rectal biopsy. The histopathology data revealed no signs of significant irritation in either the treated or the control group. There was an increased incidence of edema of the lamina propria of the rectum in both the treated and control groups. These lesions represent the mildest form of inflammation normally expected in the rectum. This mucosal inflammation is a completely reversible alteration and is probably the result of mild superficial irritation. There was no significant difference in the incidence and or severity of these changes between the treated and control groups.
The anorectal examination data revealed no signs of irritation in either treated or control group animals. The amount of mucus present in the rectum increased with time in all dogs but did not exceed minimal severity. There was no significant difference between treated and control groups in the incidence and/or degree of severity of anorectal examination.
In conclusion, these data indicated no significant rectal mucosal tissue irritation in dogs related to the daily rectal administration of 2 g of 5-aminosalicylic acid rectal suspension over a period of 27 days.