


Product Monograph - Sandostatin (Novartis Pharmaceuticals Canada, 100 mcg, 200 mcg)
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic | 11/2020 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ................................................................................ 2
TABLE OF CONTENTS ....................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................... 4
1 INDICATIONS............................................................................................................ 4
1.1 Pediatrics .......................................................................................................... 5
2 CONTRAINDICATIONS............................................................................................ 5
4 DOSAGE AND ADMINISTRATION ......................................................................... 6
4.1 Dosing Considerations ..................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment .............................................. 6
4.3 Reconstitution ................................................................................................... 8
4.4 Administration ................................................................................................... 9
5 OVERDOSAGE ....................................................................................................... 14
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............ 15
7 WARNINGS AND PRECAUTIONS ........................................................................ 16
7.1 Special Populations........................................................................................ 19
7.1.1 Pregnant Women ........................................................................................ 19
7.1.2 Breast-feeding ............................................................................................. 20
7.1.3 Pediatrics ..................................................................................................... 20
8 ADVERSE REACTIONS ......................................................................................... 20
8.1 Adverse Reaction Overview .......................................................................... 20
8.2 Clinical Trial Adverse Reactions.................................................................... 20
8.3 Less Common Clinical Trial Adverse Reactions .......................................... 26
8.5 Post-Market Adverse Reactions .................................................................... 28
9 DRUG INTERACTIONS .......................................................................................... 29
9.4 Drug-Drug Interactions................................................................................... 29
9.5 Drug-Food Interactions .................................................................................. 30
9.6 Drug-Herb Interactions................................................................................... 30
9.7 Drug-Laboratory Test Interactions................................................................. 30
10 CLINICAL PHARMACOLOGY ............................................................................... 30
10.1 Mechanism of Action................................................................................... 30
10.2 Pharmacodynamics .................................................................................... 30
10.3 Pharmacokinetics ........................................................................................ 31
11 STORAGE, STABILITY AND DISPOSAL............................................................. 32
12 SPECIAL HANDLING INSTRUCTIONS ................................................................ 32
PART II: SCIENTIFIC INFORMATION ............................................................................. 33
13 PHARMACEUTICAL INFORMATION ................................................................... 33
14 CLINICAL TRIALS .................................................................................................. 33
14.1 Trial Design and Study Demographics ...................................................... 33
14.2 Study Results .............................................................................................. 34
15 MICROBIOLOGY .................................................................................................... 36
16 NON-CLINICAL TOXICOLOGY ............................................................................. 36
PATIENT MEDICATION INFORMATION ......................................................................... 45
PATIENT MEDICATION INFORMATION ......................................................................... 53
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
SANDOSTATIN Solution for injection or infusion
General
SANDOSTATIN (octreotide acetate) therapy is indicated for control of symptoms in patients with metastatic carcinoid and vasoactive intestinal peptide-secreting tumours (VIPomas) as well as in patients with acromegaly.
Data are insufficient to determine whether SANDOSTATIN decreases the size, rate of growth, or development of metastases in patients with these tumours.
SANDOSTATIN is also indicated for the prevention of complications following pancreatic surgery in patients undergoing high-risk procedures.
SANDOSTATIN is also indicated for the emergency management of bleeding gastro-oesophageal varices in patients with cirrhosis and as protection from re-bleeding. SANDOSTATIN is used in association with specific intervention such as endoscopic sclerotherapy.
Carcinoid Tumours
SANDOSTATIN is indicated for the symptomatic treatment of metastatic carcinoid tumours where it suppresses or inhibits the severe diarrhoea and flushing episodes associated with the disease.
Vasoactive Intestinal Peptide Tumours (VIPomas)
SANDOSTATIN is indicated for the treatment of the profuse watery diarrhoea associated with VIP-secreting tumours. Significant improvement has been noted in the overall condition of these otherwise therapeutically unresponsive patients. Therapy with SANDOSTATIN results in improvement in electrolyte abnormalities, e.g., hypokalaemia, often enabling reduction of fluid and electrolyte support.
Acromegaly
SANDOSTATIN is indicated to reduce blood levels of growth hormone and IGF-1 (somatomedin C) including acromegalic patients who have had inadequate response to, or cannot be treated with surgical resection, pituitary irradiation and/or bromocriptine mesylate at maximally tolerated doses.
Since the effects of pituitary irradiation may not become maximal for several years, adjunctive therapy with SANDOSTATIN to reduce blood levels of GH and IGF-1 offers potential benefit before the effects of irradiation are manifested.
A clinically relevant growth hormone (GH) reduction (by 50% or more) occurs in almost all patients, and normalisation (plasma GH < 5 mcg/L) can be achieved in about half of the cases.
In most patients, SANDOSTATIN markedly reduces the clinical symptoms of the disease such as headache, skin and soft tissue swelling, hyperhidrosis, arthralgia, paraesthesia. In patients with a large pituitary adenoma, SANDOSTATIN treatment may result in some shrinkage of the tumour mass.
Prevention of Complications following Pancreatic Surgery
SANDOSTATIN inhibits basal and stimulated exocrine pancreatic secretion and when administered peri- and post-operatively in patients undergoing high-risk pancreatic surgery, reduces the incidence and severity of typical post-operative complications (e.g. pancreatic fistula, abscess and subsequent sepsis and post-operative acute pancreatitis).
Bleeding Gastro-oesophageal Varices
In patients presenting with bleeding gastro-oesophageal varices due to underlying cirrhosis, SANDOSTATIN administration in combination with specific intervention (e.g. sclerotherapy) provides better control of bleeding and early re-bleeding, reduces transfusion requirements and improves 5-day survival).
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
Acromegaly
SANDOSTATIN LAR is indicated for acromegalic patients who are adequately controlled with SANDOSTATIN administered subcutaneously, including those in whom surgery, radiotherapy or dopamine agonist treatment is inappropriate or ineffective, or in the interim period until radiotherapy becomes fully effective (see 4 DOSAGE AND ADMINISTRATION).
In most patients, SANDOSTATIN LAR markedly reduces the clinical symptoms of the disease, such as headache, perspiration, paraesthesia, fatigue, osteo-arthralagia and carpel tunnel syndrome.
Carcinoid Tumours
SANDOSTATIN LAR is indicated for the treatment of the severe diarrhoea and flushing episodes associated with carcinoid tumours in patients in whom symptoms are adequately controlled on subcutaneous treatment with SANDOSTATIN.
Vasoactive Intestinal Peptide Tumours (VIPomas)
SANDOSTATIN LAR is indicated for the treatment of the profuse watery diarrhoea associated with VIP-secreting tumours in patients in whom symptoms are adequately controlled on subcutaneous treatment with SANDOSTATIN.
In patients with carcinoid syndrome and VIPomas, the effect of SANDOSTATIN LAR on tumour size and rate of growth has not been determined. In patients with carcinoid syndrome and VIPomas, the effect of SANDOSTATIN LAR on development of metastases has not been determined.
1.1 Pediatrics
Paediatrics (between birth and 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for paediatric use (see 7 WARNINGS AND PRECAUTIONS, 7.4.3 Pediatrics).
1.2 Geriatrics
Information specific to the geriatric population is not available for this drug product.
2 CONTRAINDICATIONS
SANDOSTATIN and SANDOSTATIN LAR (octreotide acetate) are contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. Do not use if particulates and/or discoloration are observed.
4.2 Recommended Dose and Dosage Adjustment
SANDOSTATIN Solution for injection or infusion
Subcutaneous injection is the recommended route of administration of SANDOSTATIN for control of symptoms in most instances. Intravenous bolus injections have been used under emergency conditions. Multiple injections at the same site within short periods of time should be avoided. The initial dosage is 50 mcg, administered subcutaneously, once or twice daily. Thereafter, the number of injections and dosage may be increased gradually based on patient tolerability, clinical response and effects on levels of tumour-produced hormones (in cases of carcinoid tumours on the urinary excretion of 5-hydroxyindole-acetic acid). Dosage information for patients with specific tumours is listed below. The drug is usually given in a b.i.d or t.i.d schedule.
- Carcinoid Tumours
The suggested daily dosage of SANDOSTATIN during the first two weeks of therapy ranges from 100 to 600 mcg per day in two to four divided doses (mean daily dosage is 300 mcg). In the clinical studies, the median daily maintenance dosage was approximately 450 mcg, but clinical and biochemical benefits were obtained in some patients with as little as 50 mcg, while others required doses up to 1500 mcg per day. However, experience with doses above 750 mcg per day is limited. In the event of no beneficial response to SANDOSTATIN treatment, continuation of therapy beyond one week is not recommended.
- VIPomas
Daily dosages of 200 to 300 mcg in two to four divided doses are recommended during the initial 2 weeks of therapy (range 150 to 750 mcg) to control symptoms of the disease. On an individual basis, dosage may be adjusted to achieve a therapeutic response, but usually doses above 450 mcg per day are not required.
- Acromegaly
Daily dosages of 100 to 300 mcg b.i.d. or t.i.d. are recommended at the beginning of treatment. Dosage adjustment should be based on monthly assessment of GH levels, insulin-like growth factor 1 (IGF 1) / somatomedin C concentrations and clinical symptoms, and on tolerability. In most patients, the optimal daily dose will be 200 to 300 mcg per day. A maximum dose of 1500 mcg should not be exceeded.
If no relevant reduction of GH and IGF 1 levels and no improvement of clinical symptoms have been achieved within 3 months of starting treatment with SANDOSTATIN, therapy should be discontinued (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
- Prevention of Complications following Pancreatic Surgery
Daily dosage of 100 mcg t.i.d., administered subcutaneously, for 7 consecutive days starting on the day of the operation at least one hour before laparatomy.
- Bleeding Gastro-oesophageal Varices in patients with cirrhosis
The recommended dose of SANDOSTATIN is 25 mcg/hour by continuous intravenous infusion for 48 hours. In patients with high risk of re-bleeding, infusion should be maintained up to a maximum of 5 days.
Immediately prior to use, the contents of the ampoule or multidose vial should be diluted in physiological saline. The volume of dilution will depend on the infusion system used and should be adjusted to ensure a continuous infusion of SANDOSTATIN at the recommended rate. Once diluted, the solution should be used within 24 hours. Discard unused portion.
As with all parenteral drugs, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitation, discoloration and leakage prior to administration, whenever solution and container permit.
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
SANDOSTATIN LAR may only be administered by deep intragluteal injection. The site of repeat intragluteal injection should be alternated between the left and right gluteal muscle.
SANDOSTATIN LAR should only be administered by a trained healthcare professional. Do not directly inject diluent without preparing the suspension. It is important to closely follow the mixing instructions included in the packaging. SANDOSTATIN LAR must be administered immediately after mixing. SANDOSTATIN LAR should be administered intragluteally at 4-week intervals. Administration of SANDOSTATIN LAR at intervals greater than 4 weeks is not recommended because there is no adequate information on whether such patients could be satisfactorily controlled. Deltoid injections are to be avoided because of significant discomfort at the injection site when given in that area. SANDOSTATIN LAR should never be administered by the intravenous or subcutaneous routes. The following dosage regimens are recommended.
- Acromegaly
For patients who are adequately controlled with SANDOSTATIN s.c., it is recommended to start treatment with the administration of 20 mg SANDOSTATIN LAR at 4-week intervals for 3 months. Treatment with SANDOSTATIN LAR can be started the day after the last dose of SANDOSTATIN s.c. Subsequent dosage adjustments should be based upon serum growth hormone (GH) and insulin-like growth factor 1/somatomedin C (IGF 1) concentrations and clinical symptoms.
For patients in whom, within this 3-month period, clinical symptoms and biochemical parameters (GH, IGF 1) are not fully controlled (GH concentrations still above 2.5 mcg/L) the dose may be increased to 30 mg every four weeks.
For patients whose serum GH concentrations are consistently below 1 mcg /L, whose IGF 1 serum concentrations normalized, and in whom most reversible signs/symptoms of acromegaly have disappeared after 3 months of treatment with 20 mg, 10 mg SANDOSTATIN LAR may be administered every 4 weeks. However, particularly in this group of patients, it is recommended to closely monitor adequate control of serum GH and IGF 1 concentrations and clinical signs/symptoms at this low dose of SANDOSTATIN LAR.
For patients in whom surgery, radiotherapy or dopamine agonist treatment is inappropriate, or in the interim period until radiotherapy becomes fully effective, a short test dosing of SANDOSTATIN s.c. is recommended to assess the response and systemic tolerability of octreotide prior to initiating treatment with SANDOSTATIN LAR as described above.
- Carcinoid tumours and VIPomas
Patients not currently treated with SANDOSTATIN s.c. should begin therapy with subcutaneous SANDOSTATIN s.c. The suggested daily dose during the first 2 weeks of therapy ranges from 100-600 mcg/day in 2-4 divided doses (mean daily dose is 300 mcg). Some patients may require doses up to 1500 mcg/day. The suggested daily dose for VIPomas is 200-300 mcg in 2-4 divided doses (range 150-750 mcg); dosage may be adjusted on an individual basis to control symptoms but usually doses above 450 mcg /day are not required.
SANDOSTATIN s.c. should be continued for at least 2 weeks. Thereafter, patients who are considered “responders” to octreotide acetate and who tolerate the drug may be switched to SANDOSTATIN LAR in the dosage regimen described below.
Patients currently receiving SANDOSTATIN s.c. can be switched to SANDOSTATIN LAR in a dosage of 20 mg intragluteally at 4-week intervals for 2 months. Gluteal injection sites should be alternated to avoid irritation. Because of the need for serum octreotide to reach therapeutically effective levels following initial injection of SANDOSTATIN LAR, carcinoid tumour and VIPoma patients should continue to receive SANDOSTATIN s.c. for at least 2 weeks in the same dosage they were taking before the switch. Failure to continue s.c. injections for this period may result in exacerbation of symptoms. Some patients may require 3 or 4 weeks of such therapy.
After 2 months of a 20 mg dosage of SANDOSTATIN LAR, dosage may be increased to 30 mg every 4 weeks if symptoms are not adequately controlled. Patients who achieve good control on a 20 mg dose may have their dose lowered to 10 mg for a trial period. If symptoms recur, dosage should then be increased to 20 mg every 4 weeks. A dose of 10 mg is not recommended as a starting dose, however, because therapeutically effective levels of octreotide are reached more rapidly with a 20 mg dose.
Dosages higher than 30 mg are not recommended because there is no information on their usefulness.
Despite good overall control of symptoms, patients with carcinoid tumours and VIPomas often experience periodic exacerbation of symptoms (regardless of whether they are being maintained on SANDOSTATIN s.c. or SANDOSTATIN LAR). During these periods, they may be given SANDOSTATIN s.c. for a few days at the dosage they were receiving prior to switching to SANDOSTATIN LAR. When symptoms are again controlled, SANDOSTATIN s.c. can be discontinued.
Health Canada has not authorized an indication for paediatric use.
4.3 Reconstitution
Parenteral Products
Solution for continuous i.v. infusion: Immediately prior to use, the contents of the ampoule or multidose vial should be diluted in physiological saline. The volume of dilution will depend on the infusion system used and should be adjusted to ensure a continuous infusion of SANDOSTATIN at a rate of 25 mcg/hour. The following are examples of dilutions which may be used:
| SANDOSTATIN | Volume of physiological saline | Approximate available volume mL | Nominal concentration mcg/mL | Infusion rate mL/h (mcg/h) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Concentration mcg/mL | Size mL | Volume mL | ||||||||||||||
| 500 | 1 | 1 | 49 | 50 | 10 | 2.5 (25) | ||||||||||
| 200 | 5 | 2.5 | 47.5 | 50 | 10 | 2.5 (25) | ||||||||||
| 200 | 5 | 3 | 93 | 96 | 6.25 | 4 (25) | ||||||||||
As with all parenteral drugs, i.v. admixtures should be inspected visually for clarity, particulate matter, precipitation, discoloration and leakage prior to administration, whenever solution and container permit.
SANDOSTATIN diluted in physiological saline is stable for 24 hours when stored at room temperature. Discard unused portion.
Octreotide acetate is not stable in Total Parenteral Nutrition (TPN) solutions. It is generally not recommended to mix other medicinal products with octreotide in the same infusion bag or in the same cannula. Physical incompatibilities have been reported (e.g. with pantoprazole).
4.4 Administration
Preparation of SANDOSTATIN LAR (Octreotide for Injectable Suspension)
SANDOSTATIN LAR is supplied in kits containing:
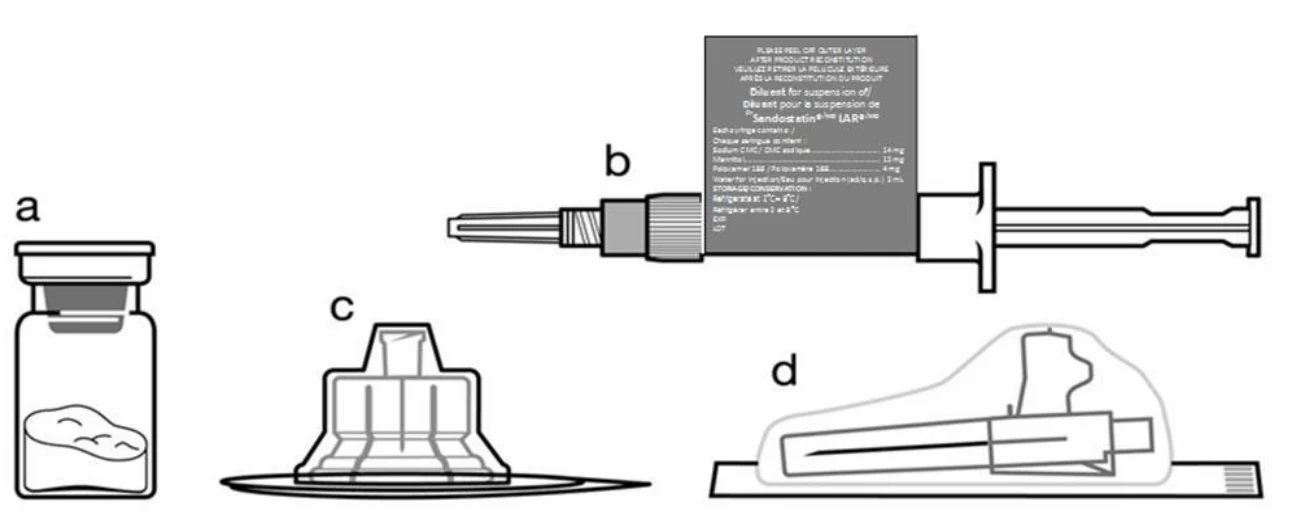
- a. One vial of SANDOSTATIN LAR 10 mg, 20 mg, or 30 mg octreotide (as acetate) for injectable suspension
- b. One prefilled syringe containing the diluent (showing the peel-off outer syringe label)
- c. One vial adapter for drug product reconstitution
- d. One 19G x 1.5” safety injection needle
- e. One instruction booklet
Follow the instructions below carefully to ensure proper reconstitution of SANDOSTATIN LAR before deep intragluteal injection.
There are 3 critical steps in the reconstitution of SANDOSTATIN LAR. Not following them could result in failure to deliver the drug appropriately.
- The kit must reach room temperature. Remove the kit from the fridge and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours.
- After adding the diluent, ensure that the powder is fully saturated by letting the vial stand for 5 minutes.
After saturation, shake the vial moderately in a horizontal direction for a minimum of
- 30 seconds until a uniform suspension is formed. The SANDOSTATIN LAR suspension must only be prepared immediately before administration. As with all parenteral admixtures, the constituted product should be examined for the presence of foreign particulate matter, agglomeration or discolouration. Any defective units should be discarded.
SANDOSTATIN LAR should only be administered by a trained health care professional.
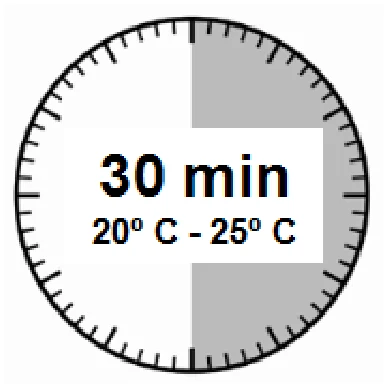 | Step 1 Remove the SANDOSTATIN LAR kit from refrigerated storage. ATTENTION: It is essential to start the reconstitution process only after the kit reaches room temperature. Let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. |
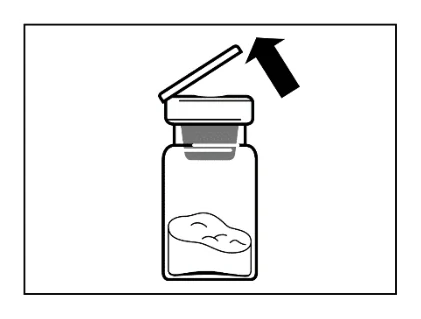 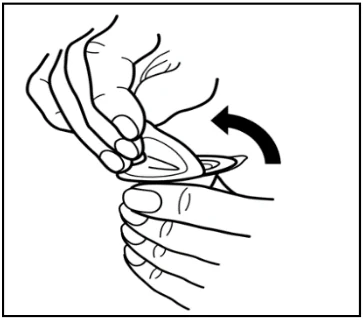 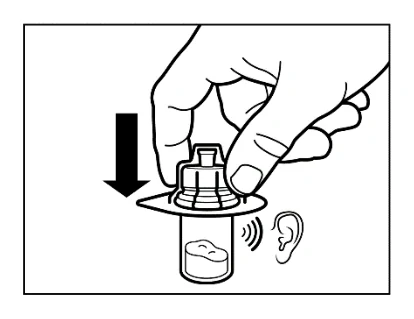 | Step 2 Remove the plastic cap from the vial and clean the rubber stopper of the vial with an alcohol wipe. Remove the lid film of the vial adapter packaging, but do NOT remove the vial adapter from its packaging. Holding the vial adapter packaging, position the vial adapter on top of the vial and push it fully down so that it snaps in place, confirmed by an audible “click.” |
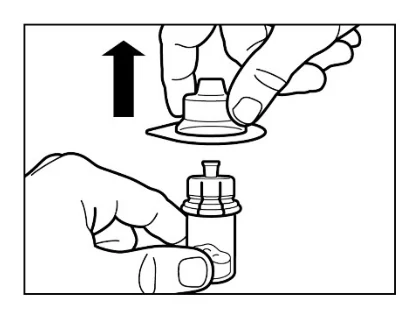 | Lift the packaging off the vial adapter with a vertical movement. |
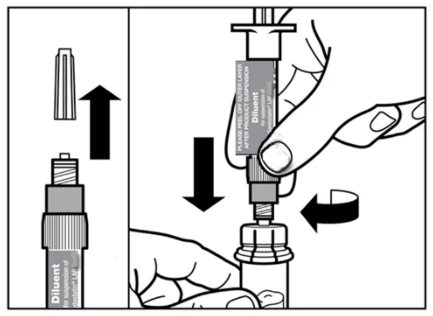 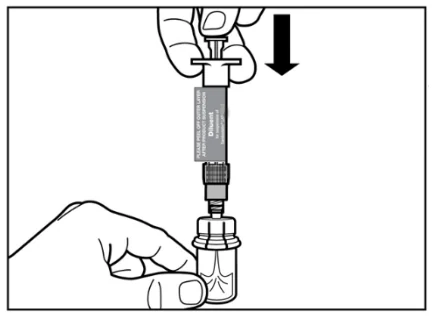 | Step 3 Remove the cap from the syringe prefilled with diluent and screw the syringe onto the vial adapter Slowly push the plunger all the way down to transfer all the diluent into the vial. |
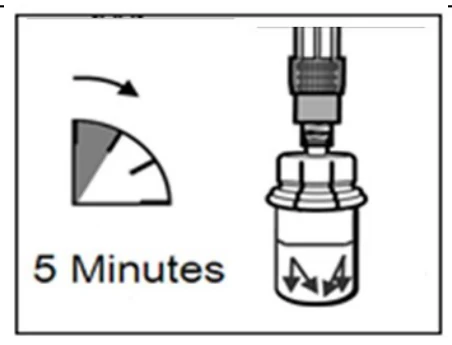 | Step 4 ATTENTION: It is essential to let the vial stand for 5 minutes to ensure that the diluent has fully saturated the powder. Note: It is normal if the plunger rod moves up, as there might be a slight overpressure in the vial. At this stage, prepare the patient for injection. |
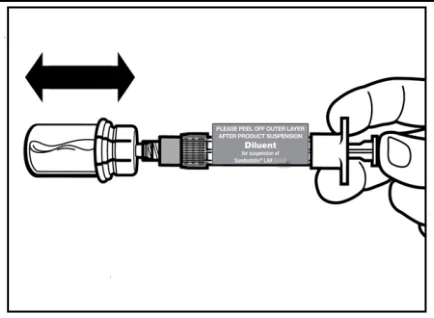 | Step 5 After the saturation period, make sure that the plunger is pushed all the way down in the syringe. ATTENTION: Keep the plunger pressed and shake the vial moderately in a horizontal direction for a minimum of 30 seconds so that the powder is completely suspended (milky uniform suspension). Repeat moderate |
| shaking for another 30 seconds if the powder is not completely suspended. | |
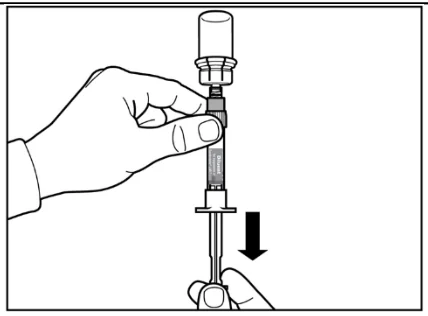 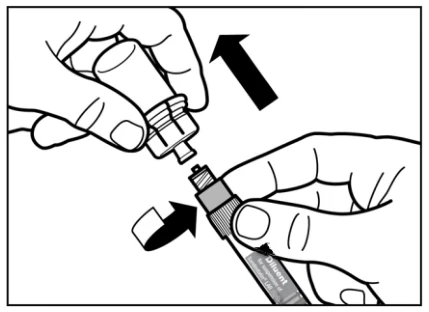 | Step 6 Prepare injection site with an alcohol wipe. Turn syringe and vial upside down, slowly pull the plunger back and draw the entire contents from the vial into the syringe. Unscrew the syringe from the vial adapter. |
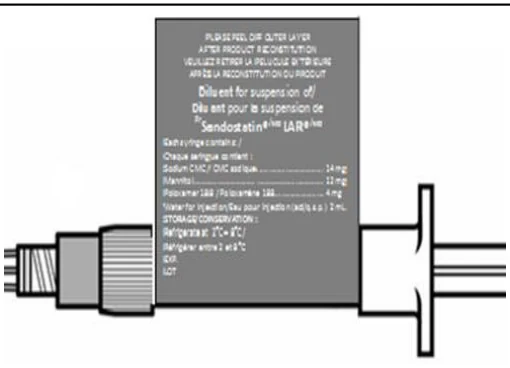 | Step 7 The product in the syringe now consists of reconstituted SANDOSTATIN LAR Octreotide (as acetate) for Injectable Suspension. To avoid confusion, peel off the outer syringe label, which corresponds only to the diluent. It is no longer a correct representation of the current contents of the syringe. |
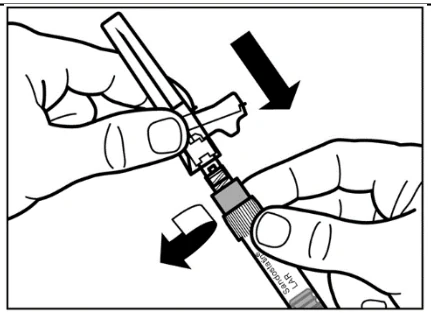 | Step 8 Screw the safety injection needle onto the syringe. Gently re-shake the syringe to ensure a milky uniform suspension. Pull the protective cover straight off the needle. |
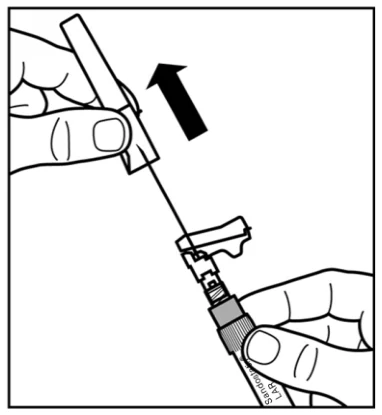 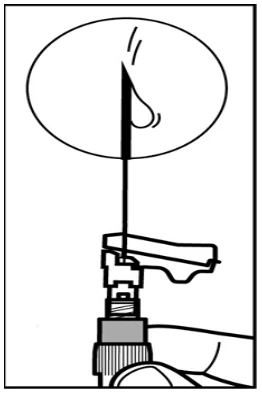 | Gently tap the syringe to remove any visible bubbles and expel them from the syringe. Verify that injection site has not been contaminated. Proceed immediately to Step 9 for administration to the patient. Any delay may result in sedimentation. |
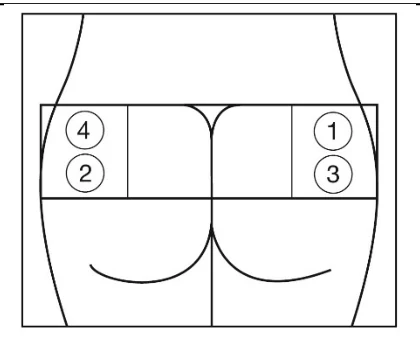 | Step 9 SANDOSTATIN LAR must be given only by deep intragluteal injection, NEVER intravenously. Insert the needle fully into the left or right gluteus at a 90º angle to the skin. Slowly pull back the plunger to check that no blood vessel has been penetrated (reposition if a blood vessel has been penetrated). Depress the plunger with steady pressure until the syringe is empty. Withdraw the needle from the injection site and activate the safety guard (as shown in Step 10). |
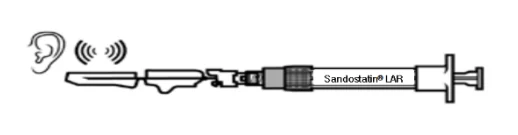
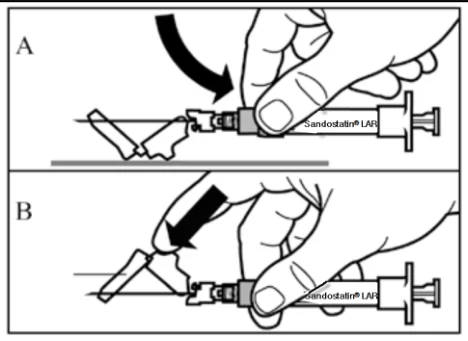 | Step 10 Activate the safety guard over the needle in one of the 2 methods shown:
An audible “click” confirms the proper activation. Dispose of syringe immediately (in a ‘sharps’ container). |
SANDOSTATIN LAR must be given only by deep intragluteal injection, never intravenously. If a blood vessel has been penetrated, another injection site must be selected. The site of repeat intragluteal injection should be alternated between the left and right gluteal muscle. Do not use the same gluteal region each time (every 4 weeks).
4.5 Missed Dose
SANDOSTATIN Solution for injection or infusion
If an injection is missed, the dose should not be doubled at the next injection.
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
If a scheduled injection is missed, the missed dose should be administered as soon as possible.
5 OVERDOSAGE
SANDOSTATIN Solution for injection or infusion
A limited number of accidental overdoses of SANDOSTATIN in adults and children have been reported. In adults, the doses ranged from 2,400-6,000 mcg/day administered by continuous infusion (100-250 mcg/hour) or subcutaneously (1,500 mcg t.i.d.). The adverse events reported were arrhythmia, hypotension, cardiac arrest, brain hypoxia, pancreatitis, hepatitis steatosis, diarrhoea, weakness, lethargy, weight loss, hepatomegaly, and lactic acidosis. Atrioventricular blocks (including complete atrioventricular block) were reported in patients receiving higher doses of continuous infusion (100 mcg/hr) and/or bolus of SANDOSTATIN intravenously (50 mcg bolus) followed by 50 mcg/hr continuous infusion).
In children, the doses ranged from 50-3,000 mcg/day administered by continuous infusion (2.1-500 mcg/hr) or subcutaneously (50-100 mcg). The only adverse event reported was mild hyperglycaemia.
No unexpected adverse events have been reported in cancer patients receiving SANDOSTATIN at doses of 3,000-30,000 mcg/day in divided doses subcutaneously.
The management of overdosage is symptomatic.
 |
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
A limited number of accidental overdoses of SANDOSTATIN LAR have been reported. The doses ranged from 100 mg to 163 mg/month of SANDOSTATIN LAR. The only adverse event reported was hot flushes.
Cancer patients receiving doses of SANDOSTATIN LAR up to 60 mg/month and up to 90 mg/2 weeks have been reported. These doses were in general well tolerated; however, the following adverse events have been reported: frequent urination, fatigue, depression, anxiety, and lack of concentration.
The management of overdosage is symptomatic. Patients who received higher than recommended doses of intravenous octreotide are at increased risk of higher degree atrioventricular blocks and should be kept under appropriate cardiac monitoring.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients | ||||
|---|---|---|---|---|---|---|
| SANDOSTATIN Solution for injection or infusion | ||||||
| Subcutaneous injection or intravenous infusion | Single dose ampoule (1 mL) | |||||
| 50 mcg/mL, 100 mcg/mL octreotide (free peptide) (present as octreotide acetate) | lactic acid: 3,400 mcg/mL mannitol: 45,000 mcg/mL water for injection: q.s. 1.0 mL | |||||
| Multidose vial (5 mL) | ||||||
| 200 mcg/mL octreotide (free peptide) (present as octreotide acetate) | lactic acid: 3,400 mcg/mL mannitol: 45,000 mcg/mL phenol: 5,000 mcg/mL water for injection: q.s. 1.0 mL | |||||
| Sodium hydrogen carbonate is added to provide a buffered solution pH 4.2 ± 0.2 | ||||||
| SANDOSTATIN LAR (Octreotide for injectable suspension) | ||||||
| Intramuscular (intragluteal) injection | 10 mg octreotide (free peptide) (11.2 mg octreotide acetate)/vial | poly (DL-lactide-co-glycolide): 188.8 mg mannitol: 41.0 mg | ||||
| 20 mg octreotide (free peptide) (22.4 mg octreotide acetate)/vial | poly (DL-lactide-co-glycolide): 377.6 mg mannitol: 81.9 mg | |||||
| 30 mg octreotide (free peptide) (33.6 mg octreotide acetate)/vial | poly (DL-lactide-co-glycolide): 566.4 mg mannitol: 122.9 mg | |||||
| Diluent (2 mL) in pre-filled glass syringe | carboxymethylcellulose sodium: 14 mg mannitol: 12 mg poloxamer 188: 4 mg water for injection: q.s. 2 mL | |||||
SANDOSTATIN
SANDOSTATIN (octreotide acetate) is supplied in 1 mL ampoules, each containing 50 mcg or 100 mcg of octreotide as acetate. SANDOSTATIN is available in boxes of 5 ampoules.
SANDOSTATIN is also available in 5 mL multidose vials. Each vial contains 1000 mcg of octreotide as acetate (200 mcg/mL).
SANDOSTATIN LAR is supplied in kits containing
- One single dose 6 mL glass vial of SANDOSTATIN LAR (Octreotide for Injectable Suspension) containing 10, 20, or 30 mg of octreotide (as acetate) slow release
- A pre-filled glass syringe containing 2 mL of diluent
- One vial adapter for drug product reconstitution
- One 19G x 1.5” safety injection needle
- An instruction booklet
7 WARNINGS AND PRECAUTIONS
General
Sudden escape from symptomatic control by SANDOSTATIN may occur infrequently, with rapid recurrence of severe symptoms. Dosage adjustment therefore may be required.
As GH-secreting pituitary tumours may sometimes expand, causing serious complications (e.g. visual field defects), it is essential that all patients treated with SANDOSTATIN s.c. or SANDOSTATIN LAR be carefully monitored. If evidence of tumour expansion appears, alternative procedures may be advisable.
Octreotide alters the balance between the counter-regulatory hormones, insulin, glucagon and growth hormone, which may result in hypoglycaemia or hyperglycaemia. Octreotide also suppresses secretion of thyroid stimulating hormone, which may result in hypothyroidism. Cardiac conduction abnormalities have also occurred during treatment with octreotide.
Careful instruction in sterile subcutaneous and intramuscular injection techniques should be given to the patients and to other persons who may administer SANDOSTATIN or SANDOSTATIN LAR injections (see PATIENT MEDICATION INFORMATION).
Patients with carcinoid tumours and VIPomas should be advised to adhere closely to their scheduled return visits for reinjection in order to minimize exacerbation of symptoms.
Patients with acromegaly should also be urged to adhere to their return visit schedule to help assure steady control of GH and IGF-1 levels.
Carcinogenesis and Mutagenesis
Studies in laboratory animals have demonstrated no mutagenic potential of octreotide acetate.
Cardiovascular
In both acromegalic and carcinoid syndrome patients, bradycardia, arrhythmias and conduction abnormalities have been reported during octreotide therapy. Dose adjustments of drugs such as beta blockers, calcium channel blockers, or agents to control fluid and electrolyte balance, may be necessary. Other EKG changes were observed such as QT prolongation, axis shifts, early repolarization, low voltage, R/S transition, early R wave progression, and non-specific ST-T wave changes. The relationship of these events to octreotide acetate is not established because many of these patients have underlying cardiac disease. In one acromegalic patient with severe congestive heart failure, initiation of SANDOSTATIN therapy resulted in worsening of CHF with improvement when drug was discontinued. Confirmation of a drug effect was obtained with a positive re-challenge (see 8 ADVERSE REACTIONS).
Endocrine and Metabolism
- Glucose Metabolism
SANDOSTATIN therapy is occasionally associated with mild transient hypo- or hyperglycaemia but may also result in overt diabetes due to alterations in the balance between the counter-regulatory hormones, insulin, glucagon and growth hormone. Patients should be closely observed on introduction of SANDOSTATIN therapy and at each change of dosage for symptomatic evidence of hyper- and hypoglycaemia. Insulin requirement of patients with type I diabetes mellitus may be reduced by administration of SANDOSTATIN. In non-diabetics and type II diabetics with partially intact insulin reserves, SANDOSTATIN administration can result in prandial increases in glycaemia. Severe hyperglycaemia, subsequent pneumonia, and death following initiation of SANDOSTATIN therapy was reported in one patient with no history of hyperglycaemia.
Predicting the effect of SANDOSTATIN on glucose tolerance in any given patients is not possible at this time. It is recommended that all acromegalic patients have their serum glucose carefully monitored during initiation and titration of therapy with SANDOSTATIN s.c. or SANDOSTATIN LAR.
Since following bleeding episodes from oesophageal varices, there is an increased risk for the development of insulin-dependent diabetes or for changes in insulin requirement in patients with pre-existing diabetes, an appropriate monitoring of blood glucose is required.
It is therefore recommended that glucose tolerance and antidiabetic treatment be periodically monitored during therapy with SANDOSTATIN s.c. or SANDOSTATIN LAR.
- Thyroid Function
Data on the effect of chronic therapy with SANDOSTATIN on hypothalamic/pituitary function have not been obtained. A progressive drop in T4 levels has been reported, culminating in clinical and biochemical hypothyroidism after 19 months of therapy in one clinical trial patient (carcinoid) receiving 1500 mcg of SANDOSTATIN s.c. daily. Minimal impairment of thyroid function was recorded in some acromegalic patients following treatment with SANDOSTATIN LAR. Therefore, baseline and periodic assessment of thyroid function (TSH, total and/or free T4) should be monitored during chronic therapy with octreotide acetate.
Gastrointestinal
- Nutrition
There is evidence that SANDOSTATIN therapy may alter absorption of dietary fats in some patients. It is suggested that periodic quantitative 72-hour faecal fat and serum carotene determinations be performed to aid in the assessment of possible drug-induced aggravation of fat malabsorption.
Depressed vitamin B12 levels and abnormal Schilling’s tests have been observed in some patients receiving octreotide therapy, and monitoring of vitamin B12 levels is recommended during therapy with SANDOSTATIN LAR.
Octreotide has been investigated for the reduction of excessive fluid loss from the G.I. tract in patients with conditions producing such a loss. If such patients are receiving total parenteral nutrition (TPN), serum zinc may rise excessively when the fluid loss is reversed. Patients on TPN and octreotide should have periodic monitoring of zinc levels.
Hepatic/Biliary/Pancreatic
- Gallbladder and Related Events
Single doses of SANDOSTATIN have been shown to inhibit gallbladder contractility and decrease bile secretion in normal volunteers. In clinical trials with SANDOSTATIN (primarily patients with acromegaly or psoriasis) in patients who had not previously received octreotide, the incidence of biliary tract abnormalities was 63% (27% gallstones, 24% sludge without stones, 12% biliary duct dilatation). The incidence of stones or sludge in patients who received SANDOSTATIN for 12 months or longer was 52%. The incidence of gallbladder abnormalities did not appear to be related to age, sex or dose but was related to duration of exposure.
In clinical trials 52% of acromegalic patients, most of whom received SANDOSTATIN LAR for 12 months or longer, developed new biliary abnormalities including gallstones, microlithiasis, sediment, sludge and dilatation. The incidence of new cholelithiasis was 22%, of which 7% were microstones.
In clinical trials 62% of malignant carcinoid patients who received SANDOSTATIN LAR for up to 18 months developed new biliary abnormalities including gallstones, sludge and dilatation. New gallstones occurred in a total of 24% of patients.
Across all trials, a few patients developed acute cholecystitis, ascending cholangitis, biliary obstruction, cholestatic hepatitis, or pancreatitis during octreotide therapy or following its withdrawal. One patient developed ascending cholangitis during SANDOSTATIN therapy and died. Despite the high incidence of new gallstones in patients receiving octreotide, 1% of patients developed acute symptoms requiring cholecystectomy. Additionally, there have been post-marketing reports of cholelithiasis (gallstones) resulting in complications including cholecystitis, cholangitis, pancreatitis, and requiring cholecystectomy in patients taking SANDOSTATIN or SANDOSTATIN LAR.
It is recommended that patients on extended therapy with SANDOSTATIN or SANDOSTATIN LAR be evaluated at baseline and periodically (at about 6-month intervals) to assess the presence of gallstones using ultrasound evaluations of the gallbladder and bile ducts (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). If complications of cholelithiasis are suspected, discontinue SANDOSTATIN or SANDOSTATIN LAR and treat appropriately.
- Liver Impairment
In patients with liver cirrhosis, the half-life of the drug may be increased, necessitating adjustment of the maintenance dosage.
Monitoring and Laboratory Tests
Laboratory tests that may be helpful as biochemical markers in determining and following patient response depend on the specific tumour. Based on diagnosis, measurement of the following substances may be useful in monitoring the progress of therapy:
Carcinoid: 5-HIAA (urinary 5-hydroxyindole acetic acid), plasma serotonin, plasma Substance P
VIPoma: VIP (plasma vasoactive intestinal peptide)
Acromegaly: Growth hormone - IGF-1 (somatomedin C)
Responsiveness to octreotide may be evaluated by determining growth hormone levels at 1-4 hour intervals for 8-12 hours after subcutaneous injection of SANDOSTATIN (not SANDOSTATIN LAR). Alternatively, a single measurement of IGF-1 (somatomedin C) level may be made two weeks after initiation of SANDOSTATIN or dosage change. After patients are switched from SANDOSTATIN to SANDOSTATIN LAR, GH and IGF-1 determinations may be made after 3 monthly injections of SANDOSTATIN LAR (steady-state serum levels of octreotide are reached only after a period of 3 months of monthly injections). Growth hormone can be determined using the mean of 4 assays taken at 1 hour intervals. Somatomedin C can be determined with a single assay. All GH and IGF-1 determinations should be made 4 weeks after the previous SANDOSTATIN LAR.
In patients with acromegaly, if no relevant reduction of GH and IGF 1 levels and no improvement of clinical symptoms have been achieved within 3 months of starting treatment with SANDOSTATIN, therapy should be discontinued.
Patients should undergo a baseline ultrasound examination of the gallbladder and bile ducts prior to commencing SANDOSTATIN treatment. Periodic ultrasound examination of the gallbladder should be performed, at about 6-month intervals, throughout SANDOSTATIN treatment. If stones are already present before the start of therapy, the potential benefit of SANDOSTATIN should be assessed against the potential risks associated with the gallstones. In case of asymptomatic gallstone, SANDOSTATIN may be continued, depending on re-assessment of the benefit/risk ratio with increased frequency of monitoring. Symptomatic gallstones should receive medical attention and be treated.
Baseline and periodic total and/or free T4 measurements should be performed during chronic therapy (see Endocrine and Metabolism, Thyroid Function).
Renal
- Renal Impairment
In patients with severe renal failure requiring dialysis, the half-life of the drug may be increased, necessitating adjustment of the maintenance dosage.
Reproductive Health: Female and Male Potential
- Fertility
The therapeutic benefits of a reduction in growth hormone (GH) levels and normalization of insulin-like growth factor 1 (IGF-1) concentration in female acromegalic patients could potentially restore fertility. Pregnancy in acromegalic patients may increase the risk of gestational diabetes, hypertension and exacerbation of the underlying cardiac disease, therefore female patients of childbearing potential should be advised to use adequate contraception during treatment with octreotide.
Animal studies in rats and rabbits did not adversely affect reproduction performance following treatment with SANDOSTATIN at doses up to 1 mg/kg/day (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
- Teratogenic Risk
There is no direct indication of a teratogenic potential following SANDOSTATIN treatment in animal studies (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. In the post-marketing experience, data on a limited number of pregnancies have been reported in patients on octreotide therapy.
7.1.2 Breast-feeding
It is not known whether octreotide is excreted in human breast milk. Animal studies have shown excretion of octreotide in breast milk. Patients should not breast-feed during SANDOSTATIN treatment.
7.1.3 Pediatrics
Experience with SANDOSTATIN s.c. and SANDOSTATIN LAR in the paediatric population is limited.
SANDOSTATIN has been primarily used in patients with congenital hyperinsulinism (also called nesidioblastosis). The youngest patient to receive the drug was 1 month old. At doses of 1-40 mcg/kg body weight/day, the majority of side effects observed were gastrointestinal - steatorrhea, diarrhoea, vomiting and abdominal distension. Poor growth has been reported in several patients treated with SANDOSTATIN for more than 1 year; catch-up growth occurred after SANDOSTATIN was discontinued. A 16-month-old male with enterocutaneous fistula developed sudden abdominal pain and increased nasogastric drainage and died 8 hours after receiving a single 100 mcg subcutaneous dose of SANDOSTATIN.
7.1.4 Geriatrics
Clinical studies of SANDOSTATIN did not include sufficient numbers of patients age 65 years and over to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most frequent adverse reactions reported with SANDOSTATIN and SANDOSTATIN LAR include gastrointestinal disorders, nervous system disorders, hepatobiliary disorders, and metabolism and nutritional disorders.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
SANDOSTATIN Solution for injection or infusion in GEP and Acromegaly
Table 1 Composite Listing of Adverse Reactions in 196 GEP Endocrine Tumour Patients and 114 Acromegalic Patients Treated with SANDOSTATIN
Adverse Reaction Profile According to Body System | GEP Endocrine Tumour Patients (n=196) % | Acromegalic Patients (n=114) % |
|---|---|---|
Gastrointestinal Diarrhea Abdominal discomfort | 6.6 4.1 | 57.9 43.9 |
Adverse Reaction Profile According to Body System | GEP Endocrine Tumour Patients (n=196) % | Acromegalic Patients (n=114) % |
|---|---|---|
Stools Loose Nausea Flatulence Constipation Abdominal distention Stools abnormal Cholelithiasis Rectal gas Vomiting Fatty stools GI bleeding Rectal disorders Hemorrhoids Cholecystitis Eructations | 3.1 8.7 0.5 1.0 - 0.5 <1.0 - 2.6 3.6 0.5 0.5 - - - | 36.0 29.8 13.2 8.8 7.9 6.1 4.4 4.4 4.4 - - - 1.8 1.8 1.8 |
Integumentary Pain at injection site Acne Bruise Pruritus Alopecia/Baldness/Hair loss | 8.2 - 0.5 - 1.0 | 9.6 4.4 4.4 4.4 3.5 |
Musculoskeletal Backache/pain Joint pain Arthritis Arm/leg heavy - tired Leg ache/pain Osteoarthritis Vertebral disk disorder Twitching | 0.5 - - - - - - - | 4.4 4.4 2.6 2.6 2.6 1.8 1.8 1.8 |
Respiratory Throat pain Flu symptoms Cold symptoms Sinusitis Nasal congestion | 0.5 - - - - | 2.6 6.1 6.1 3.5 1.8 |
Cardiovascular Leg cramps Dyspnea Epistaxis Chest pain Edema Ischemic Attack Hypertension Thrombophlebitis Cramps | - - - 0.5 1.0 0.5 0.5 0.5 - | 3.5 1.8 1.8 - 2.6 - - - 2.6 |
Adverse Reaction Profile According to Body System | GEP Endocrine Tumour Patients (n=196) % | Acromegalic Patients (n=114) % |
|---|---|---|
Autonomic Visual disturbances Mouth dry/furry/xerostomia Flushing Numbness Hot flash | 0.5 0.5 0.5 - - | 2.6 1.8 1.8 1.8 1.8 |
Central Nervous Headache Dizziness Fatigue Anxiety/Nervousness Asthenia Bell's palsy Seizure Depression Sleepiness/insomnia Weakness Moody Appetite loss Irritability Tinnitus | 1.5 1.5 1.0 0.5 0.5 0.5 0.5 0.5 0.5 1.0 - - - - | 18.4 14.9 9.6 2.6 - - - 2.6 1.8 - 2.6 1.8 1.8 1.8 |
Urogenital Urinary tract infection Pollakiuria Vagina infection Vagina itch Breast lump Dysuria Kidneys, pain in Polyuria Prostatitis Tumor breast | - - - - - - - - - - | 6.1 3.5 2.6 1.8 1.8 1.8 1.8 1.8 1.8 1.8 |
Hematologic Hematoma, injection site | - | 9.6 |
Endocrine Hypoadrenalism Hypothyroidism Hypogonadism Hypoglycemia | - - - - | 2.6 1.8 1.8 1.8 |
Miscellaneous Foot pain Fever Otitis Weight gain | - - - - | 1.8 1.8 1.8 1.8 |
Local reactions after s.c. administration of SANDOSTATIN include pain and sensations of stinging, tingling or burning at the site of injection, with redness and swelling. These rarely last more than fifteen minutes. Local discomfort may be reduced by allowing the solution to reach room temperature before injection and by slowly injecting SANDOSTATIN.
In clinical trials, acromegalic patients had a higher incidence of diarrhoea, abdominal pain/discomfort, nausea and loose stools than patients treated with SANDOSTATIN s.c. for other indications. It is believed that the primary reason for this observation is that patients who received SANDOSTATIN for carcinoid syndrome, VIPoma and other gastro-entero-pancreatic tumours had these gastrointestinal symptoms at baseline and would only report them as adverse events if they became more frequent or severe during SANDOSTATIN treatment.
The adverse event rate for SANDOSTATIN during study B301 is presented in comparison to placebo. This comparison more accurately reflects the difference in adverse event rates between SANDOSTATIN and placebo.
Table 2 Number % Patients in US Studies B301, B302, B303 with Adverse Events by Treatment and by Body System. Events occurring in ≥ 3%
| Specific Adverse Event by Body System | Placebo B301 (n=55)% | SANDOSTATIN B301 (n=60)% | SANDOSTATIN B301, B302 & B303 (n=114)% |
|---|---|---|---|
Skin Pain at injection site Acne Bruise Pruritus Alopecia/Baldness/Hair loss | 2 (3.6) -- 1 (1.1) -- -- | 5 (8.3) 2 (3.3) 2 (3.3) -- -- | 11 (9.6) 5 (4.4) 5 (4.4) 5 (4.4) 4 (3.5) |
Musculoskeletal Back ache/pain Joint pain | -- 2 (3.6) | -- 1 (1.7) | 5 (4.4) 5 (4.4) |
Respiratory Flu symptoms Cold symptoms Sinusitis | -- -- -- | 2 (3.3) 2 (3.3) -- | 7 (6.1) 7 (6.1) 4 (3.5) |
Cardiovascular Leg cramps | -- | -- | 4 (3.5) |
Hematologic Hematoma, injection site | 6 (10.9) | 1 (1.7) | 11 (9.6) |
Gastrointestinal Diarrhea Abdominal discomfort Stools Loose Nausea Flatulence Constipation Abdominal distention Stools abnormal Cholelithiasis Rectal gas Vomiting | 6 (10.9) 7 (12.7) 8 (14.5) 6 (10.9) 2 (3.6) -- -- -- -- -- 1 (1.8) | 32 (53.3) 14 (23.3) 16 (26.7) 17 (28.3) 6 (10.0) 1 (1.7) 2 (3.3) 3 (5.0) -- -- 3 (5.0) | 66 (57.9) 50 (43.9) 41 (36.0) 34 (29.8) 15 (13.2) 10 (8.8) 9 (7.9) 7 (6.1) 5 (4.4) 5 (4.4) 5 (4.4) |
Urogenital Urinary tract infection Pollakiuria | -- 2 (3.6) | 3 (5.0) 1 (1.7) | 7 (6.1) 4 (3.5) |
| Specific Adverse Event by Body System | Placebo B301 (n=55)% | SANDOSTATIN B301 (n=60)% | SANDOSTATIN B301, B302 & B303 (n=114)% |
|---|---|---|---|
Central Nervous Headache Dizziness Fatigue | 6 (10.9) 6 (10.9) 2 (3.6) | 8 (13.3) 5 (8.3) 3 (5.0) | 21 (18.4) 17 (14.9) 11 (9.6) |
Gastrointestinal side effects include anorexia, nausea, vomiting, crampy abdominal pain, abdominal bloating, flatulence, loose stools, diarrhoea and steatorrhea. Although measured faecal fat excretion may increase, there is no evidence to date that long-term treatment with SANDOSTATIN s.c. has led to nutritional deficiency due to malabsorption. In rare instances, gastrointestinal side effects may resemble acute intestinal obstruction with progressive abdominal distention, severe epigastric pain, abdominal tenderness and guarding. Occurrence of gastrointestinal side effects may be reduced by avoiding meals around the time of SANDOSTATIN s.c. administration, that is, by timing injections between meals or at bedtime.
SANDOSTATIN Solution for injection or infusion in the Prevention of Complications Following Pancreatic surgery
Local reactions at the site of injection were the most frequently reported side effects in 247 patients undergoing pancreatic surgery treated with SANDOSTATIN s.c. for 7 consecutive days starting on the day of the operation, at least 1 hour before laparatomy. Pruritus, exanthema, vomiting, biliary sludge and fever were each reported in 0.4% of patients and flushes and rash occurred in 0.8% of patients.
SANDOSTATIN Solution for injection or infusion in Bleeding Gastro-oesophageal Varices
Raised blood glucose levels were reported in 23 of 98 cirrhotic patients treated with SANDOSTATIN 25 mcg/hour administered by i.v. infusion over 5 days for the emergency management of bleeding oesophageal varices. Diarrhoea occurred in 5% of patients.
SANDOSTATIN LAR (Octreotide for Injectable Suspension) in Acromegaly
No clinical studies have been performed which compare SANDOSTATIN LAR to placebo. However, the profile of adverse reactions recorded in acromegalic patients treated with SANDOSTATIN LAR was similar to that known for SANDOSTATIN s.c. administration. Local injection site reactions to SANDOSTATIN may occur and are usually mild and of short duration. These reactions include pain, and rarely swelling and rash. In the double blind studies, gastrointestinal side effects following administration of SANDOSTATIN LAR were the most frequent adverse events and included abdominal pain, diarrhoea (loose stools), flatulence and steatorrheic stools.
Adverse events occurring in ≥ 2% of patients who participated in the major studies in acromegaly (including their long-term extensions of up to 30 months duration) are listed in the table below, by dose group. It should be noted that some patients may appear under multiple dose levels since some patients switched dose levels.
Table 3 Adverse Events Occurring in ≥ 2% of Patients Treated with SANDOSTATIN LAR
| Adverse Event | Dose Level | ||
|---|---|---|---|
10 mg n=57 (%) | 20 mg n=233 (%) | 30 mg n=129 (%) | |
Application Site Injection site pain Injection site reaction | 1.8 -- | 9.0 2.1 | 10.9 3.9 |
Body as a whole Influenza-like symptoms Fatigue Pain Surgery Back pain Asthenia Edema Malaise Accidental trauma Hot flushes Tumor nos. Fever | 8.8 3.5 1.8 3.5 1.8 3.5 1.8 1.8 3.5 -- -- -- | 10.3 5.2 5.6 2.1 3.4 1.3 3.0 1.3 1.3 2.6 0.9 0.9 | 17.8 11.6 2.3 6.2 2.3 4.7 1.6 3.9 2.3 1.6 3.1 3.1 |
Cardiovascular Hypertension | 1.8 | 9.9 | 7 |
CNS & Peripheral Headache Dizziness Paresthesia Cramps Vertigo | 7.0 5.3 1.8 1.8 3.5 | 8.6 6.0 3.4 3.4 1.7 | 12.4 10.1 7.0 3.9 1.6 |
Gastrointestinal Diarrhea Abdominal Pain Flatulence Constipation Nausea Vomiting Dyspepsia Steatorrhea Feces discoloured Tenesmus | 7.0 12.3 12.3 14.0 3.5 1.8 1.8 5.3 -- -- | 21.5 15.0 12.4 8.2 4.3 3.0 3.0 1.3 2.6 0.9 | 30.2 25.6 23.3 14.7 7.8 6.2 3.9 4.7 3.9 3.9 |
Liver & Biliary Cholelithiasis Gall bladder disorder | 3.5 -- | 7.3 3.9 | 12.4 7.0 |
Musculoskeletal Arthralgia Arthropathy Myalgia Back pain Pain leg(s) | -- -- 1.8 -- 3.5 | 2.6 3.0 2.1 3.0 0.9 | 6.2 4.7 3.9 0.8 0.8 |
| Adverse Event | Dose Level |
|---|
10 mg n=57 (%) | 20 mg n=233 (%) | 30 mg n=129 (%) | |
|---|---|---|---|
Psychiatric Disorder Insomnia Anxiety Depression Somnolence Nervousness | 3.5 -- -- 1.8 -- | 3.9 1.3 2.1 0.4 0.4 | 1.6 4.7 1.6 2.3 2.3 |
Resistance mechanism Infection viral abscess Infection | 1.8 -- 1.8 | 2.6 2.1 1.7 | 3.9 1.6 2.3 |
Respiratory System URTI Coughing Pharyngitis Rhinitis Bronchitis Respiratory disorder Sinusitis | 3.5 1.8 1.8 -- 1.8 1.8 1.8 | 3.4 4.3 4.3 -- 3.0 1.3 0.9 | 4.7 3.1 3.1 5.4 1.6 3.1 2.3 |
Urinary System UTI Cystitis Dysuria Micturition frequency | 1.8 -- -- -- | 2.1 0.9 0.4 -- | 3.1 2.3 2.3 2.3 |
Skin & Appendages Sweating increased Pruritus Alopecia Rash erythematosus Rash | 1.8 1.8 1.8 -- 3.5 | 3.4 1.3 0.9 2.6 -- | 4.7 4.7 3.9 0.8 -- |
Other Anemia Conjunctivitis Ear disorder Menstrual disorder Neoplasm, surgery | 5.3 -- -- -- -- | 6.4 2.1 -- 1.3 -- | 17.1 3.1 2.3 2.3 2.3 |
Descriptions of Selected Adverse Reactions
Liver and Biliary
SANDOSTATIN and other somatostatin analogues have been shown to inhibit gallbladder contractility and decrease bile secretion, which can lead to gallbladder abnormalities or sludge. Prolonged use of SANDOSTATIN s.c. or SANDOSTATIN LAR may result in gallstone formation (see 7 WARNINGS AND PRECAUTIONS). Pancreatitis may develop in patients on long-term treatment with SANDOSTATIN who develop cholelithiasis.
There have been isolated reports of hepatic dysfunctions associated with SANDOSTATIN s.c. and SANDOSTATIN LAR administration. These consist of the following:
- acute hepatitis without cholestasis and normalization of transaminase values on withdrawal of SANDOSTATIN s.c. has occurred;
- the slow development of hyperbilirubinemia in association with elevation of alkaline phosphatase, gamma glutamyl transferase and, to a lesser extent, transaminases.
Endocrine
Because of its inhibitory action on growth hormone, glucagon and insulin, SANDOSTATIN s.c. or SANDOSTATIN LAR may impair glucose regulation. Postprandial glucose tolerance may be impaired and in some instances, with chronic administration, a state of persistent hyperglycaemia may be induced. Hypoglycaemia has also been observed.
Pancreatitis
Acute pancreatitis has been reported in rare instances. Generally, this effect is seen within the first hours or days of SANDOSTATIN s.c. treatment and resolves on withdrawal of the drug.
Hypersensitivity and anaphylactic reactions
Hypersensitivity reactions have been reported; most hypersensitivity and allergic reactions affect the skin and rarely affect the mouth and airways.
Isolated reports of anaphylactic reaction have been reported. SANDOSTATIN administered s.c. and to a much lesser degree by i.v. infusion, can lead to hypersensitivity reaction that may range from generalized pruritus to cardiovascular shock or bronchospasm, with one case of death having been reported.
Cardiac disorder
Cases of bradycardia have been reported (frequency: common). In patients who are predisposed by having relatively low pre-treatment heart rates or whose cardiovascular system is already compromised, as in cirrhotic patients with bleeding oesophageal varices, it is of importance that physicians be alerted to the possible undesirable effect of bradycardia. Tachycardia has also been observed (frequency: uncommon).
Other
Rarely, hair loss has been reported in patients receiving SANDOSTATIN s.c. and SANDOSTATIN LAR treatment.
Rarely, dehydration has been reported.
8.3 Less Common Clinical Trial Adverse Reactions
Other adverse events (regardless of relationship) occurring at a 1% ≥ incidence < 2% reported in the major studies in acromegaly (all doses combined):
Body As a Whole: Oedema peripheral, syncope
Cardiovascular: Hypertension aggravated
Central and Peripheral Nervous Systems: Cramps, vertigo, neuralgia, cramps legs, neuropathy, hyperkinesia
Endocrine: Growth hormone overproduction, hypothyroidism, goiter
Gastro-intestinal System: Gastritis, haemorrhoids, gastroenteritis, haemorrhage rectum, hernia, eructation, gastro-intestinal disorder, stomatitis ulcerative
Hearing and Vestibular: Deafness, ear discharge
Heart Rate and Rhythm: Tachycardia
Liver and Biliary: Hepatitis, liver fatty
Metabolic and Nutritional: Weight increase, hypoglycaemia
Musculo-skeletal System: Arthrosis, surgery, bone fracture, osteonecrosis
Platelet, Bleeding and Clotting Epistaxis
Psychiatric: Amnesia, sleep disorder
Red Blood Cell: Anaemia hypochromic
Reproductive Disorders: Female: Breast pain female, intermenstrual bleeding, lactation non purperal. Male: prostate disorder
Resistance Mechanism: Moniliasis, otitis media, pharyngitis, tonsilitis, herpes simplex, herpes zoster
Respiratory System: Dyspnoea, pneumonia
Skin and Appendages: Skin disorder, skin dry, acne, nail disorder
Urinary System: Urinary tract infection, cystitis, dysuria, micturition frequency
Vascular (Extracardiac): Phlebitis, cerebrovascular, vein varicose
SANDOSTATIN LAR (Octreotide for Injectable Suspension) in Carcinoid Tumours
No clinical studies have been performed which compare SANDOSTATIN LAR to placebo. However, the profile of adverse reactions recorded in patients with carcinoid tumours treated with SANDOSTATIN LAR was similar to that known for SANDOSTATIN s.c. administration. In a 6-month study during which patients with carcinoid tumours were treated with either SANDOSTATIN LAR i.m. at 4-week intervals or SANDOSTATIN s.c. t.i.d., gastrointestinal side effects were the most frequently reported adverse events in both groups and included abdominal pain, diarrhoea (loose stools), constipation, flatulence nausea and vomiting. The incidences of these adverse events were similar between the 10, 20 and 30 mg dosages of SANDOSTATIN LAR.
Local injection site reactions to SANDOSTATIN may occur and are usually mild and of short duration. These reactions include pain, and rarely swelling and rash. Post-Market Adverse Reactions
Spontaneously reported adverse drug reactions are presented below. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or clearly establish a causal relationship to SANDOSTATIN or SANDOSTATIN LAR exposure.
| Cardiac disorders | Arrhythmias |
| Blood and lymphatic system disorders | Thrombocytopenia* |
| Gastrointestinal motility disorder | Ileus, intestinal obstruction |
| Hepato-biliary disorders | Acute pancreatitis, acute hepatitis without cholestasis, cholestatic hepatitis, cholestasis, jaundice, cholestatic jaundice, cholelithiasis, cholecystitis, cholangitis and pancreatitis, |
| which have sometimes required cholecystectomy | |
| Hypersensitivity | Anaphylaxis, allergy/hypersensitivity reactions |
| Investigations | Increased alkaline phosphatase levels, increased gamma glutamyl transferase level |
| Skin and subcutaneous tissue disorders | Urticaria |
* Most reports of thrombocytopenia were in patients with liver cirrhosis treated with SANDOSTATIN (i.v.) and some reports were with SANDOSTATIN LAR. This was reversible.
9 DRUG INTERACTIONS
9.2 Drug interactions overview
Many patients with carcinoid syndrome or VIPomas being treated with SANDOSTATIN s.c. have also been, or are being, treated with many other drugs to control the symptomatology or progression of the disease, generally without serious drug interaction. Included are chemotherapeutic agents, H2 antagonists, antimotility agents, drugs affecting glycemic states, solutions for electrolyte and fluid support or hyperalimentation, anti-hypertensive diuretics and anti-diarrheal agents.
Where symptoms are severe and SANDOSTATIN therapy is added to other therapies used to control glycaemic states, such as sulfonylureas, insulin and diazoxide, to beta-blockers, calcium channel blockers or to agents for the control of fluid and electrolyte balance, patients must be monitored closely and adjustment made in the other therapies as the symptoms of the disease are controlled. Evidence currently available suggests these imbalances in fluid and electrolytes or glycaemic states are secondary to correction of pre-existing abnormalities and not to a direct metabolic action of SANDOSTATIN. Adjustment of the dosage of drugs, such as insulin, affecting glucose metabolism may be required following initiation of SANDOSTATIN therapy in patients with diabetes.
9.4 Drug-Drug Interactions
Since SANDOSTATIN has been associated with alterations in nutrient absorption, its effect on absorption of any orally administered drugs should be carefully considered. A single case of transplant rejection episode (renal/whole pancreas) in a patient immunosuppressed with cyclosporine has been reported. SANDOSTATIN treatment to reduce exocrine secretion and close a fistula in this patient resulted in decreases in blood levels of cyclosporine and may have contributed to the rejection episode. SANDOSTATIN has also been found to delay the intestinal absorption of cyclosporine or cimetidine.
Concomitant administration of octreotide and bromocriptine increases the bioavailability of bromocriptine.
Limited published data indicate that somatostatin analogues might decrease the metabolic clearance of compounds known to be metabolized by cytochrome P450 enzymes, which may be due to the suppression of growth hormone. Since it cannot be excluded that octreotide may have this effect, other drugs mainly metabolized by the CYP 3A4 and which have a low therapeutic index should therefore be used with caution (e.g. cyclosporine).
Concomitant use with radioactive somatostatin analogues
Somatostatin and its analogues, such as octreotide, competitively bind to somatostatin receptors and may interfere with the efficacy of radioactive somatostatin analogues.
The administration of SANDOSTATIN LAR should be discontinued for at least 4 weeks prior to the administration of lutetium (177Lu) oxodotreotide (LUTATHERATM), a radiopharmaceutical binding to somatostatin receptors. If necessary, patients may be treated with short acting somatostatin analogues until 24 hours prior to the administration of lutetium (177Lu) oxodotreotide.
After administration of lutetium (177Lu) oxodotreotide, treatment with SANDOSTATIN LAR can be resumed within 4 to 24 hours and should be discontinued again 4 weeks prior to the next administration of lutetium (177Lu) oxodotreotide.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
No known interference exists with clinical laboratory tests, including amine or peptide determinations.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
General
Octreotide acetate is a synthetic octapeptide analogue of naturally occurring somatostatin with similar pharmacological effects, but with a prolonged duration of action. It inhibits pathologically increased secretion of growth hormone (GH) and of peptides and serotonin produced within the gastro-entero-pancreatic (GEP) endocrine system.
In normal healthy subjects, octreotide acetate has been shown to inhibit:
- Release of growth hormone (GH) stimulated by arginine infusion, exercise and insulin-induced hypoglycaemia.
- Postprandial release of insulin, glucagon, gastrin, other peptides of the GEP endocrine system, and arginine-stimulated release of insulin and glucagon.
Thyrotropin releasing hormone (TRH) stimulated release of thyroid stimulating hormone (TSH). The precise mode of action of octreotide acetate on portal hypertension is still unclear. It is thought to reduce splanchnic blood flow primarily by inhibiting vasoactive gastro-intestinal hormone secretion and exerting a direct vasomotor effect on splanchnic vessels, thus reducing portal blood flow. Using human sephanous veins, it has been shown that vasoconstriction is mediated by type 2 somatostatin receptors.
10.2 Pharmacodynamics
The pharmacological activities of octreotide acetate in man include inhibition of stimulated GH secretion, stimulated TSH levels, insulin and glucagon release, gut hormone secretion, and decreased portal hypertension. This spectrum of activity resembles that obtained with administration of somatostatin in man.
The actions of somatostatin are mediated by receptors. Five somatostatin receptor subtypes have been identified. Octreotide displays a high affinity for type 2 receptors, a moderate affinity for type 3 and 5 receptors and a very low affinity for type 1 and 4 receptors.
10.3 Pharmacokinetics
SANDOSTATIN Solution for injection or infusion
In man, octreotide acetate is rapidly and completely absorbed after s.c. injection. Peak plasma concentrations reached after s.c. administration are about half of those obtained after intravenous (i.v.) administration of the same dose. Plasma protein binding is about 65%. The uptake in red blood cells is negligible. After i.v. administration there are two disposition half-lives, a short one of about 10 minutes and a longer one of about 1.5 hours. After s.c. administration to healthy volunteers, the final disposition half-life is about 1.5 hours, the volume of distribution is 6 L and the total body clearance is about 160 mL/min. The absolute bioavailability of octreotide acetate calculated after s.c. administration was rather variable, with values of about 100% for 100 mcg and about 130% for 50 mcg and 200 mcg. There is no significant accumulation under conditions of repeated s.c. administration.
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
In patients with acromegaly, SANDOSTATIN LAR, a galenical formulation of octreotide consisting of microspheres for depot suspension suitable for repeat intramuscular administration at intervals of four weeks, delivers consistent and therapeutic octreotide serum concentrations thus consistently lowering GH and normalizing IGF-1 serum concentrations in the majority of patients.
In patients with carcinoid tumours and Vasoactive Intestinal Peptide Tumours (VIPomas), treatment with SANDOSTATIN LAR provides continuous control of symptoms related to the underlying disease.
The pharmacokinetic profile of octreotide acetate after injection of SANDOSTATIN LAR reflects the release profile from the polymer matrix and its biodegradation. Once released into the systemic circulation, octreotide distributes according to its known pharmacokinetic properties as described above for SANDOSTATIN administered subcutaneously.
After single intramuscular injections of SANDOSTATIN LAR, the serum octreotide concentration reaches a transient initial peak within one hour after administration followed by progressive decrease to a low undetectable octreotide level within 24 hours. After this initial peak on the first day, octreotide remains at sub-therapeutic levels in the majority of patients for the following seven days. Thereafter, octreotide concentrations increase again, and reach plateau concentrations around day 14 and remain relatively constant during the following three to four weeks. The peak level during day 1 is lower than levels during the plateau phase and no more than 0.5% of the total drug release occurs during day 1. After about day 42, the octreotide concentration decreases slowly, concomitantly with the terminal degradation phase of the polymer matrix dosage form.
In patients with acromegaly, plateau octreotide concentrations after single doses of 10 mg, 20 mg and 30 mg of SANDOSTATIN LAR are 358, 926 and 1710 pg/mL, respectively. Steady state octreotide concentrations reached after 3 injections at 4-week intervals, are higher by a factor of approximately 1.6 to 1.8, reaching 1557 and 2384 pg/mL after multiple injections of 20 and 30 mg SANDOSTATIN LAR, respectively. No accumulation of octreotide beyond that expected from overlapping release profiles occurred over a period of up to 28 monthly SANDOSTATIN LAR injections.
In patients with carcinoid tumours, the mean octreotide serum concentrations after six doses of 10 mg, 20 mg and 30 mg of SANDOSTATIN LAR administered by intramuscular injection every four weeks were 1231 pg/mL, 2620 pg/mL and 3928 pg/mL, respectively. Concentrations were dose proportional and steady-state concentrations were reached after two injections of 20 and
30 mg and after three injections of 10 mg.
11 STORAGE, STABILITY AND DISPOSAL
SANDOSTATIN Solution for injection or infusion
Ampoules: For prolonged storage, SANDOSTATIN ampoules must be stored at 2 to 8 ºC. Keep container in the outer carton in order to protect from light. Do not freeze.
Multidose Vials: For prolonged storage, SANDOSTATIN multidose vials must be stored at 2 to 8 ºC. Keep container in the outer carton in order to protect from light. Do not freeze.
For day-to-day use, both the ampoules and the multidose vials may be stored at room temperature for up to 2 weeks; they must be protected from light. The ampoules should be opened just prior to administration and any unused portion discarded.
Keep in a safe place out of reach of children and pets.
SANDOSTATIN LAR (Octreotide for Injectable Suspension)
The SANDOSTATIN LAR vials must be stored at 2 to 8 ºC. Keep vial in the outer carton in order to protect it from light. The vials can remain at room temperature on the day of the injection. However, the suspension must only be prepared immediately prior to i.m. injection.
Store the pre-filled syringe with 2 mL diluent at 2 to 8 ºC. Do not freeze.
The SANDOSTATIN LAR powder, once suspended in the diluent, should be used immediately.
Keep in a safe place out of reach of children and pets.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: octreotide acetate
Chemical name: D-Phenylalanyl-L-hemicystyl-L-phenylalanyl-D-tryptophyl-L-lysyl-L threonyl-L-hemicystyl-L-threoninol cyclic(2→7) disulfide acetate
Molecular formula and molecular mass: C49H66N10O10S2, x CH3COOH, 1019.3 x 60.05
Structural formula:
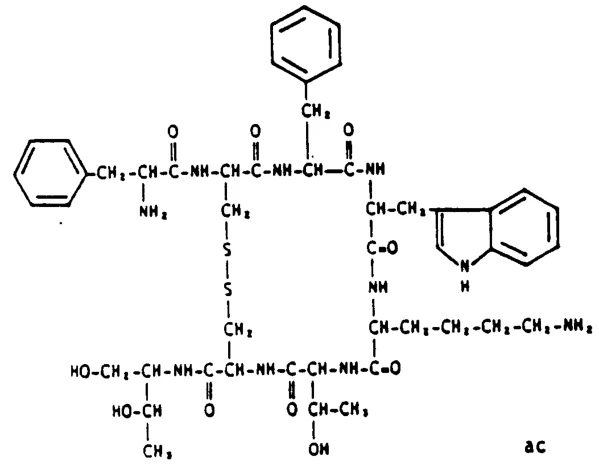
Physicochemical properties: Octreotide acetate is a bridged octapeptide analogue of somatostatin. It is a white to off-white amorphous lyophilisate, which melts with decomposition; it is very hygroscopic.
The values for pka (I) and pka (II) in water are 7.00 and 10.15 respectively. At 25°C, the solubility of octreotide acetate is > 10 mg/mL in water; > 10 mg/mL in glacial acetic acid and > 10 mg/mL in methanol.]
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The clinical trials of SANDOSTATIN LAR (octreotide acetate for injectable suspension) were performed in patients who had been receiving subcutaneous SANDOSTATIN (octreotide acetate) for a period of weeks to as long as 10 years. The acromegaly studies with SANDOSTATIN LAR described below were performed in patients who achieved GH levels of < 10 ng/mL (and, in most cases < 5 ng/mL) while on subcutaneous SANDOSTATIN. However, some patients enrolled were partial responders to subcutaneous SANDOSTATIN, i.e., GH levels were reduced by > 50% on subcutaneous SANDOSTATIN Injection compared to the untreated state, although not suppressed to < 5 ng/mL.
14.2 Study Results
Acromegaly
SANDOSTATIN LAR was evaluated in three clinical trials in acromegalic patients.
In two of the clinical trials, a total of 101 patients were entered who had, in most cases, achieved a GH level < 5 ng/mL on SANDOSTATIN given in doses of 100 mcg or 200 mcg t.i.d. Most patients were switched to 20 mg or 30 mg doses of SANDOSTATIN LAR given once every 4 weeks for up to 27 to 28 injections. A few patients received doses of 10 mg and a few required doses of 40 mg. Growth hormone and IGF-1 levels were at least as well controlled with SANDOSTATIN LAR as they had been on SANDOSTATIN and this level of control remained for the entire duration of the trials.
A third trial was a 12-month study that enrolled 151 patients who had a GH level < 10 ng/mL after treatment with SANDOSTATIN (most had levels < 5 ng/mL). The starting dose of SANDOSTATIN LAR was 20 mg every 4 weeks for 3 doses. Thereafter, patients received 10 mg, 20 mg or 30 mg every 4 weeks, depending upon the degree of GH suppression. (The recommended regimen for these dosage changes is described under 4 DOSAGE AND ADMINISTRATION.) Growth hormone and IGF-1 were at least as well controlled on SANDOSTATIN LAR as they had been on SANDOSTATIN s.c.
Table 4 summarizes the data on hormonal control (GH and IGF-1) for those patients in the first two clinical trials who received all 27 to 28 injections of SANDOSTATIN LAR.
Table 4 Hormonal Response in Acromegalic Patients Receiving 27 to 28 Injections During1 Treatment with SANDOSTATIN LAR
| SANDOSTATIN s.c. | SANDOSTATIN LAR | |||||||
| Mean Hormonal Level | N | % | N | % | ||||
| GH | < 5.0 ng/mL | 69/88 | 78 | 73/88 | 83 | |||
| < 2.5 ng/mL | 44/88 | 50 | 41/88 | 47 | ||||
| < 1.0 ng/mL | 6/88 | 7 | 10/88 | 11 | ||||
| IGF-1 normalized | 36/88 | 41 | 45/88 | 51 | ||||
| GH | < 5.0 ng/mL + IGF-1 normalized | 36/88 | 41 | 45/88 | 51 | |||
| < 2.5 ng/mL + IGF-1 normalized | 30/88 | 34 | 37/88 | 42 | ||||
| < 1.0 ng/mL + IGF-1 normalized | 5/88 | 6 | 10/88 | 11 | ||||
| 1 Average of monthly levels of GH and IGF-1 over the course of the trials | ||||||||
For the 88 patients in Table 4, a mean GH level of < 2.5 ng/mL was observed in 47% receiving SANDOSTATIN LAR. Over the course of the trials 42% of patients maintained mean growth hormone levels of < 2.5 ng/mL and mean normal IGF-1 levels.
Table 5 summarizes the data on hormonal control (GH and IGF-1) for those patients in the third clinical trial who received all 12 injections of SANDOSTATIN LAR.
Table 5 Hormonal Response in Acromegalic Patients Receiving 12 Injections During1 Treatment with SANDOSTATIN LAR
| SANDOSTATIN s.c. | SANDOSTATIN LAR | |||||||
|---|---|---|---|---|---|---|---|---|
| Mean Hormonal Level | N | % | N | % | ||||
| GH | < 5.0 ng/mL | 116/122 | 95 | 118/122 | 97 | |||
| < 2.5 ng/mL | 84/122 | 69 | 80/122 | 66 | ||||
| < 1.0 ng/mL | 25/122 | 21 | 28/122 | 23 | ||||
| IGF-1 normalized | 82/122 | 67 | 82/122 | 67 | ||||
| GH | < 5.0 ng/mL + IGF-1 normalized | 80/122 | 66 | 82/122 | 67 | |||
| < 2.5 ng/mL + IGF-1 normalized | 65/122 | 53 | 70/122 | 57 | ||||
| < 1.0 ng/mL + IGF-1 normalized | 23/122 | 19 | 27/122 | 22 | ||||
| 1 Average of monthly levels of GH and IGF-1 over the course of the trials | ||||||||
For the 122 patients in Table 5, who received all 12 injections in the third trial, a mean GH level of < 2.5 ng/mL was observed in 66% receiving SANDOSTATIN LAR. Over the course of the trial 57% of patients maintained mean growth hormone levels of < 2.5 ng/mL and mean normal IGF-1 levels. In comparing the hormonal response in these trials, note that a higher percentage of patients in the third trial suppressed their mean GH to < 5 ng/mL on subcutaneous SANDOSTATIN, 95%, compared to 78% across the two previous trials.
In all three trials, GH, IGF-1, and clinical symptoms were similarly controlled on SANDOSTATIN LAR as they had been on SANDOSTATIN.
Of the 25 patients who completed the trials and were partial responders to SANDOSTATIN (GH > 5.0 ng/mL but reduced by > 50% relative to untreated levels), 1 patient (4%) responded to SANDOSTATIN LAR with a reduction of GH to < 2.5 ng/mL and 8 patients (32%) responded with a reduction of GH to < 5.0 ng/mL.
Two exploratory open label phase IV studies investigated a 24- and 48-week treatment with SANDOSTATIN LAR in previously untreated acromegalic patients. The median reduction in tumour volume was 20.6% in Study B2402 at 24 weeks (n=46) and 29.2% at 48 weeks (n=29), and 24.5% in Study B2401 at 24 weeks (n=91) and 36.2% at 48 weeks (n=84). The percentage change in tumour volume during the course of the investigation was assessed by MRI for the intent-to-treat population. However, the clinical significance has not been established.
Carcinoid Tumours and Vasoactive Intestinal Peptide Tumours (VIPomas)
A 6-month clinical trial of malignant carcinoid syndrome was performed in 93 patients who had previously been shown to be responsive to SANDOSTATIN. Sixty-seven patients were randomized at baseline to receive, double-blind, doses of 10 mg, 20 mg or 30 mg SANDOSTATIN
LAR every 28 days and 26 patients continued, unblinded, on their previous SANDOSTATIN regimen (100-300 mcg t.i.d.).
In any given month after steady-state levels of octreotide were reached, approximately 35%-40% of the patients who received SANDOSTATIN LAR required supplemental subcutaneous SANDOSTATIN therapy usually for a few days, to control exacerbation of carcinoid symptoms. In any given month, the percentage of patients randomized to subcutaneous SANDOSTATIN who required supplemental treatment with an increased dose of SANDOSTATIN, was similar to the percentage of patients randomized to SANDOSTATIN LAR. Over the six-month treatment period approximately 50%-70% of patients who completed the trial on SANDOSTATIN LAR required subcutaneous SANDOSTATIN supplemental therapy to control exacerbation of carcinoid symptoms, although steady-state serum SANDOSTATIN LAR levels had been reached.
Table 6 presents the average number of daily stools and flushing episodes in malignant carcinoid patients.
Table 6 Average No. of Daily Stools and Flushing Episodes (ITT Population)
Daily Stools (Average No.) | Daily Flushing Episodes (Average No.) | |||||||||||
| Treatment | N | Baseline | Last Visit | Baseline | Last Visit | |||||||
| SANDOSTATIN s.c. | 26 | 3.7 | 2.6 | 3.0 | 0.5 | |||||||
| SANDOSTATIN LAR | ||||||||||||
| 10 mg | 22 | 4.6 | 2.8 | 3.0 | 0.9 | |||||||
| 20 mg | 20 | 4.0 | 2.1 | 5.9 | 0.6 | |||||||
| 30 mg | 24 | 4.9 | 2.8 | 6.1 | 1.0 | |||||||
Overall, mean daily stool frequency was as well controlled on SANDOSTATIN LAR as on SANDOSTATIN (approximately 2 to 2.5 stools/day).
Mean daily flushing episodes were similar at all doses of SANDOSTATIN LAR and on SANDOSTATIN (approximately 0.5 to 1 episode/day).
In a subset of patients with variable severity of disease, median 24-hour urinary 5-HIAA (5-hydroxyindole acetic acid) levels were reduced by 38%-50% in the groups randomized to SANDOSTATIN LAR.
The reductions are within the range reported in the published literature for patients treated with octreotide (about 10%-50%).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Single intravenous injections of SANDOSTATIN (octreotide acetate) were administered to mice and rats. Animals were observed until death occurred or for a period of seven days following administration.
| Species | LD50, mg/kg |
| Mouse | 72 (64 - 82) |
| Rat | 18 (15 - 21) |
Octreotide acetate caused no unusual effects. Immediately after administration, the following signs were observed: numbness, strained and sometimes slower breathing, jumping, and roll and stretch cramps. The animals which died, did so within one hour, the survivors were without signs after two days.
Subchronic and Chronic Toxicity
| Species | Duration | Route | Dose (mg/kg/d) | Observations |
| Rats | 4 weeks | i.p. | 1.0, 4.0, 16.0 | Low dose: Slightly↓ feed intake, slight ↑ in serum alkaline phosphatase (SAP) values Mid-dose: ↓ weight gain & feed intake, slight ↑ in urine volume & SAP, ↓ serum albumin High Dose: Moderate↓ in weight gain and feed intake, ↓ serum albumin, with slight ↑ in α2-globulin, slight ↓ in serum glucose, slight ↑ in SGOT and SAP values, unilateral, small, soft testes in 2 M, inhibited spermiogenesis with atrophy of germinal epithelium of seminiferous tubules in 3 M. NOAEL: 4 mg/kg/day |
| Dogs | 4 weeks | i.v. | 0.2, 0.8, 3.2 | Low dose: Sporadic diarrhoea, occasional prolapse of nictitating membrane, hypersalivation Mid dose: Diarrhoea, occasional prolapse of nictitating membrane, howling on injection, hyperemia of the skin of the head. High dose: Frequent diarrhoea, occasional prolapse of nictitating membrane, hypersalivation, hyperaemia of the skin of the head, slight weight loss, slight↑ in urine specific gravity NOAEL: 0.2 mg/kg/day |
| Rats | 26 weeks | i.p. | 0.02, 0.1, 1.0 | Low dose: No significant findings Mid dose: No significant findings High dose: ↓ feed intake & urine volume ↑ specific gravity of urine in F. NOAEL: 1 mg/kg/day |
| Dogs | 26 weeks + 4 week recovery | i.v. | 0.01, 0.05, 0.5 | Low dose: Sporadic diarrhoea, sporadic emesis. Scattered single cell necrosis of acidophils, pituitary gland in one F. Mid dose: Frequent diarrhoea, sporadic emesis. Pituitary findings as above in 1 F High dose: Sporadic emesis. Pituitary findings as above in 1 F and 1M All groups: Additional investigation concentrating on determining the nature of the affected pituitary cell showed that octreotide acetate-treated recovery dogs stained positively for prolactin and negatively for growth hormone. Furthermore, plasma levels of prolactin, growth hormone and 17β estradiol were unaffected by octreotide acetate treatment. |
| Species | Duration | Route | Dose (mg/kg/d) | Observations |
| Dogs | 52 weeks | s.c. | 0.24, 0.80, 1.25 | Low and mid doses: ↓ lactate dehydrogenase (M) High dose: ↓ lactate dehydrogenase (M & F). 4 M died due to large tissue masses at the injection sites. All available information at present indicates that the findings are species-specific and have no significance to the use of SANDOSTATIN in humans. All groups: ↓ body weight and body weight gain. Local irritation at the injection site (alopecia, encrustation and thickening/swelling of the skin). ↓ creatinine kinase and aspartate amino transferase. ↑alkaline phosphatases (F) and glucose; ↓ sodium levels; total protein, albumin and α globulin; bilirubin and calcium (F). Urinalysis: ↓ specific gravity and osmolarity; ↑ volume and pH in F only. Microscopically: ↑ incidence of inflammation and haemorrhage of the cutis/subcutis and skin - Abscesses. Sarcomas at the injection sites noted only at 1.25 mg/kg/day. This lesion is considered to be treatment-related. Since the development of sarcomas in sites after repeated injection over long periods of time in rats is a well-known effect, these sarcomas are considered to be expression of a chronic irritant effect of the test article at the high dose level, rather than a direct oncogenic effect. |
| Dogs | 52 weeks | s.c. | 0.05, 0.15, 0.30 | Low dose: Transient ↓ in food intake in M at start of treatment. Mid dose: Transient ↓ in food intake in M at the start of treatment and ↓ mean body weight gain in M & F; slight but persistent↓ in total protein levels (F at week 52). High dose: Transient ↓ in food intake in M at start of the treatment and ↓ mean body weight gain in M & F; slight but persistent ↓ in total protein levels (F); high incidence of diarrhoea in one F (relationship with treatment not clearly established); ↓ in pancreas weight in M (relationship with the treatment unclear). Mid & high doses: ↓ in β phase elimination half-life noted after prolonged administration. Finding may be related to the formation of antibodies to octreotide acetate. No such observations noted in single dose experiments. |
| Species | Duration | Route | Dose (mg/kg/d) | Observations |
| Rat | 104 weeks | s.c. | 0.25, 0.80, 1.25 | Control: Microscopically observed sarcomas of the skin/subcutis not as severe as treatment groups Low dose: ↓ body weight gain from week 7 in F. Microscopically observed sarcomas of the skin/subcutis not as severe high dose group. Mid dose: ↓ body weight & body weight gain and ↑relative food consumption in M. Microscopically observed sarcomas of the skin/subcutis not as severe high dose group. High dose: ↓ body weight & body weight gain throughout study and ↑ relative food consumption (more severe in M than F). Microscopically observed sarcomas of the skin/subcutis. All groups (including control): Signs of local irritation at injection site including alopecia, encrustations, scabs and thickening/swelling of skin. Microscopically observed ↑ incidence of inflammation, fibrosis, necrosis and haemorrhage associated with s.c. masses. |
Additional Toxicity Studies
| Species | Duration | Route | Dose (mg/kg/d) | Observations |
|---|---|---|---|---|
| Dogs | 3 weeks | i.v. | 0.1 (0.05 b.i.d.) | Treatment: Moderate to severe diarrhoea, ↓ body weight & feed intake. Little variation in basal levels of prolactin or growth hormone. Recovery (staggered recovery periods from 1 to 35 days): Sections of the pituitary revealed development of proliferation foci and heaped nuclei reaching a maximum at 7 days recovery, no longer apparent at day 35 of recovery. Scattered degenerated cells apparent only on days 21 and 35 of recovery. |
| Monkey (Rhesus)- 6F | 3 weeks | i.v. | 1.0 (0.5 b.i.d) | Treatment & Recovery periods: No clinical findings attributable to treatment. No diarrhoea, no alterations in basal values of plasma GH, PRL or glucose. Pituitary gland showed no morphological alterations. No treatment related findings in other organs. Electron microscopy revealed no treatment-related alterations in the pituitary. |
| Dogs | 26 weeks | i.v. | 0.5 | Treatment: Diarrhoea Recovery period (staggered from 6 hours to 12 weeks with 2 animals per period): Focal proliferation and single cell necrosis of pituitary gland. Pituitary function test (dogs treated with an injection of pituitary releasing factor during 1, 8 and 16 weeks of recovery): significant inhibition of stimulated GH release from pituitary up to 8th recovery week; by 14th week, GH response similar to control values. |
Chronic Toxicity Studies with SANDOSTATIN LAR
| Species | Duration | Route | N/dose | Dose | Observations |
| Rat/CR-SD | 26 weeks 17 weeks (recovery) | i.m. bilateral injection into biceps femoris muscles | 15M/15F 15M (recovery) | 0, 2.5 mg in 0.5 mL 0.5% sodium CMC every 4 weeks | All groups (including controls): No deaths and no drug related signs or changes in clinical pathology parameters. Reversible granulomatous myositis at injection sites. Benign haemangiomas at injection site. This is related to the i.m. injection of the Microspheres of SANDOSTATIN LAR |
| Rat/CR-SD | 24 weeks 39 weeks (recovery) | i.m. | 50M | 0, 2.5 mg | 2.5 mg group: ↓ body weights compared to controls. This finding was not present at the end of recovery period. All groups: No treatment related findings. No hyperplastic or neoplastic findings and no haemangiomas at injection sites. |
Carcinogenicity
The results of the oncogenicity studies in rats and mice do not indicate a direct carcinogenic effect of octreotide acetate and are not considered an impediment for human use.
| Species | Duration | Route | N/dose | Dose (mg/kg/d) | Observations |
| Rats (KFM-han Wistar) | 116 weeks | s.c. | 60M 60F | Placebo, NaCl 0.9%, 0.24, 0.80, 1.25 | Mid & high dose: Marginal but statistically significant ↑ in the relative proportion of lymphocytes by 10 to 8% on average in M of mid & high dose groups, and by 16% on average in F of high group, when compared with the controls. Dose-related ↓ in body weight gain in F All groups: No treatment-related differences in inter-current mortality and food intake. Except for the ↑ incidence of injection site nodule (high dose M in particular) and reproductive tract masses/nodules (high dose F), the macroscopic lesions findings did not distinguish treated from control rats. Fast-growing masses at injection sites, particularly in neck region of M. At 1.25 mg/kg/day and 0.24 mg/kg/day, these masses were recorded earlier and at a higher frequency than in other groups of M. They were identified as subcutaneous sarcomata. Alopecia, crusts, sore spots and (scabbed) wounds at the injection sites of both sexes with a higher incidence in the mid & high dose groups. Dose related ↑ in incidence of ovarian sections without corpora lutea. Within the uterus: dose related ↑ in glandular dilatation and ↑ incidence of luminal dilatation (particularly high dose group) when compared to controls. Endometritis observed in all of the treated groups (particularly high dose), but not the controls. |
| Mice (KFM-han NMRI) | 85/86 weeks (F) 98/99 weeks (M) | s.c. | 60M 60F | Placebo, NaCl 0.9%, 0.1, 0.4, 1.2, 2.0 | 0.4, 1.2 & 2 mg/kg/d: ↑ incidence of duodenal mucosal hyperplasia (F) frequently associated with inflammation and duodenal dilatation. All treated-groups: No effect in inter-current mortality, on clinical signs or nodules and masses, food consumption and body weight development. No change in differential blood count. No treatment related change in macroscopical findings. Non neoplastic lesions at the injection sites identical to those observed in control groups. Neoplastic lesions at the injection sites identical to these observed in control groups. |
Genotoxicity
In vitro mutagenicity was tested in Salmonella typhimurium strains TA1535, TA1537, TA1538, TA98 and TA100 in the presence and absence of a rat liver S9 homogenate (Ames test). No mutagenic effect was found.
In vivo mutagenicity was investigated by means of the micronucleus test using adult CD mice (Charles River). Octreotide acetate was administered intravenously twice within 24 hours. Doses were 5, 16 or 50 mg/kg for each treatment. Controls received the diluent only. Micronuclei were evaluated in bone marrow preparations made 48 or 72 hours after the first administration. Octreotide acetate was not mutagenic in this test system.
In a second in vivo mutagenicity test, damage to germ cell DNA was evaluated using the unscheduled DNA systhesis (UDS) technique. Male CD mice were injected intravenously with single doses of either 25 or 50 mg/kg. One hour after the administration of octreotide acetate, the mice received an intra-testicular injection of radioactive marked thymidine. Sperm were taken from the cauda epididymis at various time intervals, counted, and tested for radioactivity in a scintillation counter. In this test system octreotide acetate had no effect on the DNA of germ cells. The SANDOSTATIN LAR microspheres were devoid of mutagenic potential when tested in a validated in vitro bacterial assay.
Reproductive and Developmental Toxicology
Rats and rabbits were treated intravenously with SANDOSTATIN (octreotide acetate) 0.01, 0.1 or 1 mg/kg/day from day 6 to 15 or 6 to 18 post coitum. Dams and their foetuses were sacrificed at term and examined. In rats and rabbits the 0.01 mg/kg/day dose was well tolerated by the dams but the mid and high doses caused slight dose-dependent weight gain inhibition. No adverse effect on the reproduction data or foetal and placental weight was observed. Morphological findings in foetuses of both species gave no indication of a teratogenic potential of the drug.
In a peri- and post-natal study in rats treated subcutaneously with doses of 0.02, 0.1 or 1.0 mg/kg/day from day 15 post coitum until autopsy on day 21 post-partum, octreotide acetate was well tolerated by the F0 females of all treatment groups, although slightly lower weight gain during pregnancy was noted in the high dose group. The reduced growth observed in rat pups was most likely a direct consequence of the drug's main pharmacological action, i.e. growth hormone inhibition.
In a fertility and general reproduction performance study in female rats treated subcutaneously, once daily, with doses of 0.02, 0.1 or 1 mg/kg/day, octreotide acetate was well tolerated by the F0 dams of the lower and mid dose group. In the high dose group, body weight gain was slightly reduced during the 2 weeks preceding mating and there was localized hair loss at the site of injection. Reproduction performance was normal at all dose levels. Prenatal and post-natal development of F1 offspring was not affected except for some growth retardation. The reproduction performance of F1 animals as well as the development of the F2 offspring were also normal.
Animal studies do not indicate direct or indirect harmful effects with respect to pregnancy, embryonal/foetal development, parturition or postnatal development apart from some transient retardation of physiological growth.
Special Toxicology
Special Toxicity Studies with SANDOSTATIN LAR - Local Tolerance
| Species | Duration | Route | N/dose | Dose | Observations |
| Rat/CD | Single dose | i.m. bilateral (gastrocnemius muscle) | 18M 9M (Control) | 0, 20 mg in 0.2 mL 0.5% sodium CMC | Animals sacrificed sequentially at 9 time points between day 2 and day 92. Microencapsulated octreotide acetate well tolerated with no treatment related clinical signs or findings. No difference in response at injection site between diluent control and drug loaded microspheres. |
Rat CR/CD | Single dose | i.m. injection (gastrocnemius muscle) | 7M | Control (LAR microsphere diluent); 2 mg | One animal per group sacrificed on days 5, 15, 30, 45, 60, 75 and 90. No adverse histologic findings at injection sites and no difference in muscle histopathology or pattern of microcapsule degradation. |
Rabbit NZW | Single dose | i.m. bilateral (sacrospinalis muscles) | 9M | 0, 25 mg (in 2.0 mL 0.5% sodium CMC) | Animals sacrificed sequentially at 9 time points between day 2 and day 92. Microencapsulated octreotide acetate well tolerated with no treatment-related clinical signs or mortality. No difference in response at injection site between diluent control and drug loaded microspheres. |
Rabbit NZW | Single dose | i.m. | 7M | Control (LAR microsphere diluent), 25 mg | One animal per group sacrificed on days 5, 15, 30, 45, 60, 75 and 90. No difference in response between diluent control and drug loaded microspheres. |