


Product Monograph - Signifor Lar
Recent Major Label Changes
| 2025-05 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................. 2
Table of Contents ................................................................................................................. 2
Part 1: Health Professional Information ................................................................................ 5
- 1.
Indications ................................................................................................................ 5
1.1. Pediatrics ................................................................................................................ 5
1.2. Geriatrics ................................................................................................................ 5
- 2. Contraindications ...................................................................................................... 5
- 3. Serious Warnings and Precautions Box ...................................................................... 6
- 4.
Dosage and Administration ....................................................................................... 6
4.1. Dosing Considerations ........................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment ...................................................... 7
4.3. Reconstitution ........................................................................................................ 8
4.4. Administration ..................................................................................................... 13
4.5. Missed Dose ......................................................................................................... 13
- 5. Overdose ................................................................................................................ 13
- 6. Dosage Forms, Strengths, Composition and Packaging ............................................. 14
- 7.
Warnings and Precautions ....................................................................................... 14
Cardiovascular .................................................................................................................. 14
Driving and Operating Machinery .................................................................................... 15
Endocrine and Metabolism .............................................................................................. 16
Gastrointestinal ................................................................................................................ 18
Hematologic ..................................................................................................................... 18
Hepatic/Biliary/Pancreatic ............................................................................................... 19
Monitoring and Laboratory Tests .................................................................................... 21
Renal ................................................................................................................................ 22
Reproductive Health: ....................................................................................................... 22
7.1. Special Populations .............................................................................................. 22
7.1.1. Pregnancy ......................................................................................................... 22
7.1.2. Breastfeeding ................................................................................................... 23
7.1.3. Pediatrics .......................................................................................................... 23
7.1.4. Geriatrics .......................................................................................................... 23
- 8.
Adverse Reactions ................................................................................................... 23
8.1. Adverse Reaction Overview ................................................................................. 23
8.2. Clinical Trial Adverse Reactions ........................................................................... 24
8.3. Less Common Clinical Trial Adverse Reactions .................................................... 34
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 36
8.5. Post-Market Adverse Reactions ........................................................................... 39
- 9.
Drug Interactions .................................................................................................... 39
9.2. Drug Interactions Overview ................................................................................. 39
9.3. Drug-Behavioural Interactions ............................................................................. 40
9.4. Drug-Drug Interactions ........................................................................................ 40
9.5. Drug-Food Interactions ........................................................................................ 42
9.6. Drug-Herb Interactions ........................................................................................ 42
9.7. Drug-Laboratory Test Interactions....................................................................... 42
- 10.
Clinical Pharmacology ............................................................................................. 42
10.1. Mechanism of Action ....................................................................................... 42
10.2. Pharmacodynamics .......................................................................................... 43
10.3. Pharmacokinetics ............................................................................................. 47
- 11. Storage, Stability and Disposal ................................................................................. 49
- 12. Special Handling Instructions ................................................................................... 50
Part 2: Scientific Information .............................................................................................. 51
- 13. Pharmaceutical Information .................................................................................... 51
- 14.
Clinical Trials ........................................................................................................... 52
14.1. Clinical Trials by Indication .............................................................................. 52
- 15. Microbiology ........................................................................................................... 59
- 16. Non-Clinical Toxicology ........................................................................................... 60
Patient Medication Information ......................................................................................... 63
Part 1: Health Professional Information
1. Indications
SIGNIFOR LAR (pasireotide) is indicated for the treatment of adult patients with:
- acromegaly for whom surgery is not an option or has not been curative.
- Cushing’s disease for whom surgery is not an option or for whom surgery has failed, as long as clinical benefit or normalization of urinary free cortisol (UFC) (or >50% decrease in UFC) are derived (see 14.1 Clinical Trials by Indication, Cushing’s disease).
The 60 mg dose is only to be used for the treatment of acromegaly (see 4. Dosage and Administration).
SIGNIFOR LAR should be prescribed and supervised by a qualified physician.
1.1. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3. Pediatrics).
1.2. Geriatrics
Geriatrics (≥65 years of age): There are limited data on the use of SIGNIFOR LAR in acromegaly patients and very limited data in Cushing’s disease patients older than 65 years. Clinical studies of SIGNIFOR LAR did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients (see 7.1.4. Geriatrics).
2. Contraindications
SIGNIFOR LAR is contraindicated in:
- Patients with moderate or severe hepatic impairment (Child Pugh B or C).
- Patients with uncontrolled diabetes (≥8% HbA1c while receiving anti-diabetic therapy).
Patients with the following cardiovascular conditions:
- NYHA Class III to IV heart failure
- Cardiogenic shock
- Second or third degree atrioventricular (AV) block, sinoatrial block, or sick sinus syndrome (unless patient has a functioning pacemaker)
- Severe bradycardia
- Congenital long QT syndrome or baseline QTc interval ≥500 ms.
- Patients who are hypersensitive to pasireotide or to any ingredient in the formulation including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
RISK OF HEPATOTOXICITY:
RISK OF CARDIOVASCULAR (CV) ADVERSE EVENTS (AEs):
RISK OF HYPERGLYCEMIA:
|
4. Dosage and Administration
4.1. Dosing Considerations
Prior to the start of SIGNIFOR LAR, patients should have the following baseline evaluations (see 7. Warnings and Precautions):
- Fasting Plasma Glucose
- Hemoglobin A1c
- Liver tests
- Electrocardiogram
- Gallbladder ultrasound
SIGNIFOR LAR is contraindicated in patients with uncontrolled diabetes mellitus (see 2. Contraindications).
4.2. Recommended Dose and Dosage Adjustment
Acromegaly
The recommended initial dose of SIGNIFOR LAR for the treatment of acromegaly is 40 mg administered by deep intramuscular injection every 4 weeks (q28d).
The dose may be increased to a maximum of 60 mg for patients whose GH and/or IGF-1 levels are not fully controlled after 3 months of treatment with SIGNIFOR LAR at 40 mg and who tolerate this dose (see 8. Adverse Reactions, Acromegaly and 14.1 Clinical Trials by Indication, Acromegaly).
Management of suspected adverse reactions or over response to treatment (age and sex adjusted IGF-1 < LLN) may require dose reduction of SIGNIFOR LAR. The dose may be decreased, either temporarily or permanently, by 20 mg decrements. Efficacy should be monitored closely as there are limited data with the use of the 20 mg dose.
Cushing’s disease
The recommended initial dose of SIGNIFOR LAR for the treatment of Cushing’s disease is 10 mg administered by deep intramuscular injection every 4 weeks (q28d).
Patients should be evaluated for treatment response after the first month of treatment and periodically thereafter (see 7 Warnings and Precautions – Monitory and Laboratory Tests, Cushing’s disease). The dose may be titrated every 2 to 4 months based on response and tolerability (see 8. Adverse Reactions, Cushing’s disease and 14.1 Clinical Trials by Indication, Cushing's disease). The maximum dose of SIGNIFOR LAR in Cushing’s disease is 40 mg q28d. If no clinical benefit is observed at the maximum tolerated dose, the patient should be considered for discontinuation.
Management of suspected adverse reactions or over-response to treatment (e.g., cortisol levels less than the lower limit of normal range or in the low part of the normal range in patients with symptoms suggestive of adrenal insufficiency) may require dose reduction to the previous tolerated dose, interruption, or discontinuation of SIGNIFOR LAR. For patients treated with 10 mg once every 28 days, the dose may be either interrupted or discontinued (see 7. Warnings and Precautions – Endocrine and Metabolism, Hypocortisolism and Monitoring and Laboratory Tests, Hypocortisolism).
Switch from subcutaneous to intramuscular formulation in Cushing’s disease
There are no clinical data available on switching from the subcutaneous to the intramuscular pasireotide formulation. If such a switch would be considered, the recommended initial dose for the treatment of Cushing’s disease is 10 mg of SIGNIFOR LAR administered by deep intramuscular injection once every 4 weeks. The patient should be monitored for response and tolerability, and further dose adjustment, interruption, or discontinuation may be required.
Special populations
Renal impairment
No dose adjustment is required in patients with mild to moderate renal impairment. In a clinical study of single dose pasireotide s.c. 900 µg, in patients with various degrees of renal impairment, grade 3 and grade 4 increases in amylase, lipase, and uric acid and grade 3 decreases in hemoglobin were observed in subjects with severe renal impairment and ESRD. SIGNIFOR LAR should be used with caution in patients with severe renal impairment and ESRD (see 7. Warnings and Precautions - Renal, Monitoring and Laboratory Tests, 4.2 Recommended Dose and Dosage Adjustment, and 10. Clinical Pharmacology).
Hepatic impairment
Dose adjustment is not required in patients with mildly impaired hepatic function (Child-Pugh A). SIGNIFOR LAR is contraindicated in patients with moderate or severe hepatic impairment (Child Pugh B or C) (see 2. Contraindications and 7. Warning and Precautions).
Pediatric patients (<18 years of age)
The safety and efficacy of SIGNIFOR LAR in patients under 18 years of age have not been established. Health Canada has not authorized an indication for pediatric use. SIGNIFOR LAR should not be used in pediatric patients (see 1.1 Pediatrics and 7.1.3 Pediatrics).
Geriatric patients (≥65 years of age)
There are limited data on the use of SIGNIFOR LAR in patients older than 65 years (see 1.2 Geriatrics and 7.1.4. Geriatrics). Generally, dose selection for elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
4.3. Reconstitution
PARENTERAL PRODUCT FOR DEEP INTRAMUSCULAR INJECTION ONLY
ATTENTION: There are 2 critical steps in the reconstitution of SIGNIFOR LAR. Not following them could result in failure to deliver the drug appropriately.
|
Included in the injection kit:
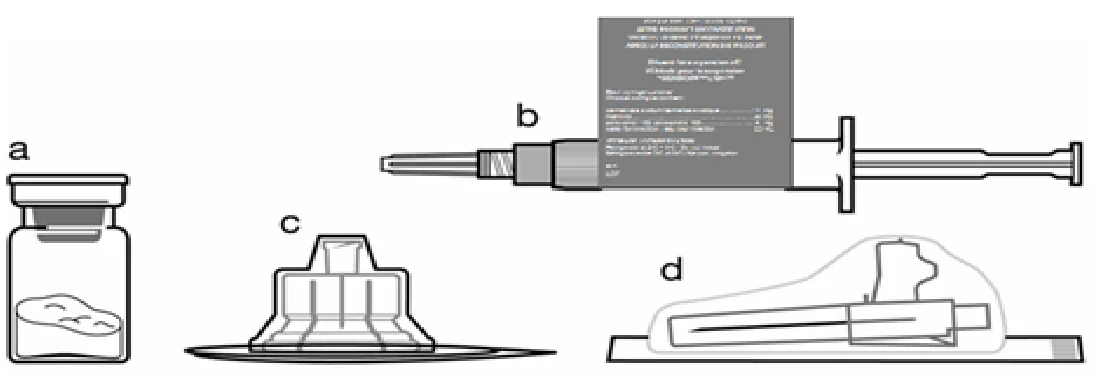
a. One vial containing SIGNIFOR LAR powder 20mg, 40mg, or 60 mg pasireotide for injectable suspension
b. One prefilled syringe containing the diluent solution for reconstitution (showing the peel-off outer syringe label)
c. One vial adapter for drug product reconstitution
d. One safety injection needle (20G x 1.5”)
e. One instruction booklet
f. The package insert
Follow the instructions below carefully to ensure proper reconstitution of SIGNIFOR LAR before deep intramuscular injection.
SIGNIFOR LAR suspension must only be prepared immediately before administration.
SIGNIFOR LAR should only be administered by a trained health care professional.
Step 1 Remove the SIGNIFOR LAR injection kit from refrigerated storage. ATTENTION: It is essential to start the reconstitution process only after the injection kit reaches room temperature. Let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. Note: The injection kit can be re-refrigerated if needed but should not be refrigerated after reconstitution. | 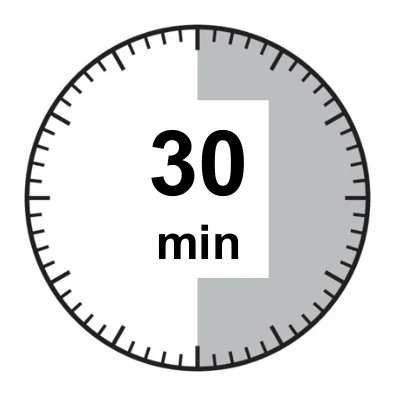 30 min |
Step 2 Remove the plastic cap from the vial and clean the rubber stopper of the vial with an alcohol wipe. | 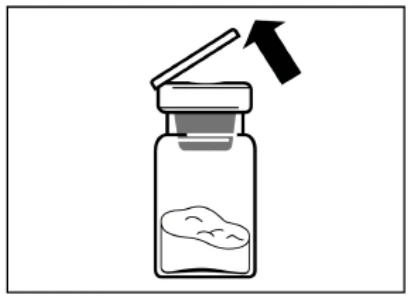 |
Place the package on a clean and flat surface. Remove the lid film of the vial adapter packaging, but do NOT remove the vial adapter from its packaging. Holding the vial adapter packaging, position the vial adapter on top of the vial and push it fully down so that it snaps in place, confirmed by an audible “click”. | 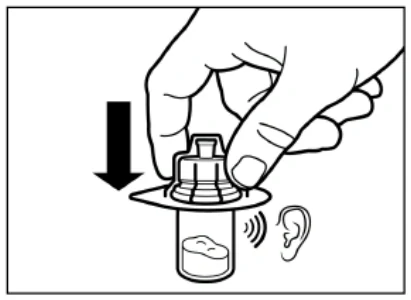 |
| Hold the vial firmly and lift the packaging off the vial adapter with a vertical movement. | 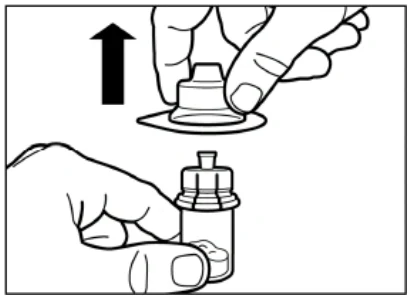 |
Step 3 Remove the cap from the syringe prefilled with diluent solution and screw the syringe clockwise onto the vial adapter. | 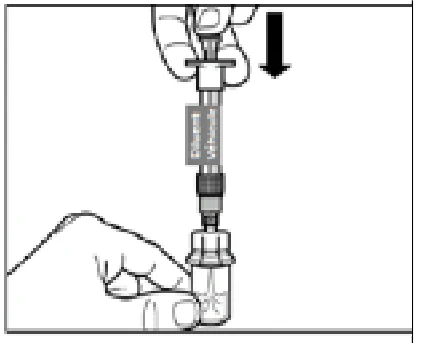 |
| Slowly push the plunger all the way down to transfer all the diluent solution in the vial. | 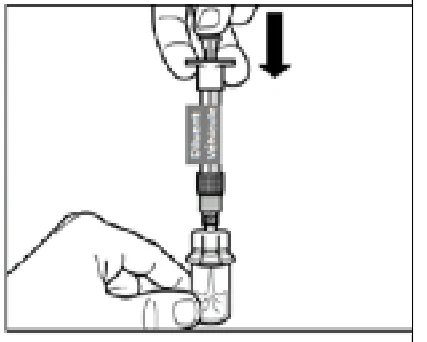 |
Step 4 ATTENTION: Keep the plunger pressed and shake the vial moderately in a horizontal direction for a minimum of 30 seconds so that the powder is completely suspended. Repeat moderate shaking for another 30 seconds if the powder is not completely suspended. | 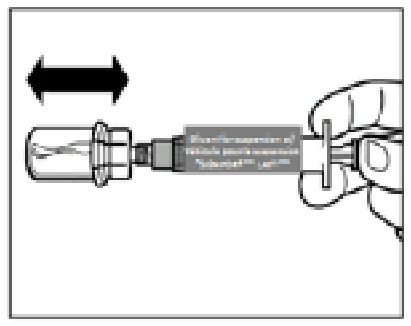 |
Step 5 Turn syringe and vial upside down, slowly pull the plunger back and draw the entire content from the vial into the syringe. | 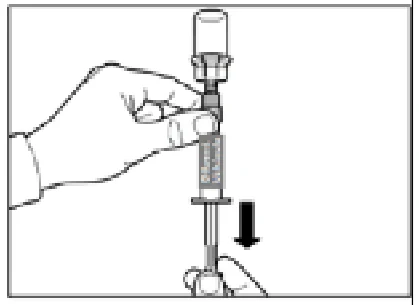 |
| Unscrew the syringe counterclockwise from the vial adapter. Ensure that the tip of the syringe remains sterile | 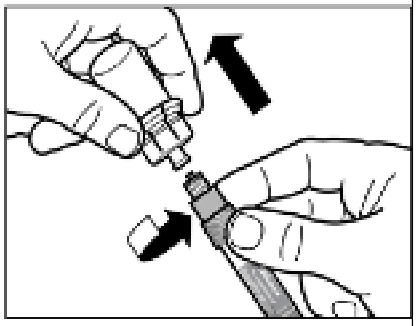 |
Step 6 The product in the syringe now consists of reconstituted SIGNIFOR LAR for Injectable Suspension. The suspension should be milky, slightly yellowish to yellowish and homogeneous To avoid confusion, peel off the outer syringe label which corresponds only with the diluent. It is no longer a correct representation of the current contents of the syringe. | 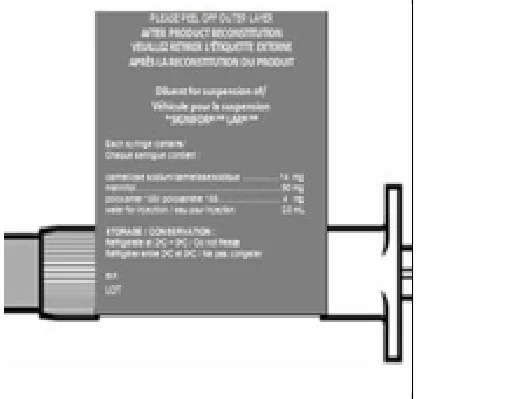 |
Step 7 Screw the safety injection needle onto the syringe. | 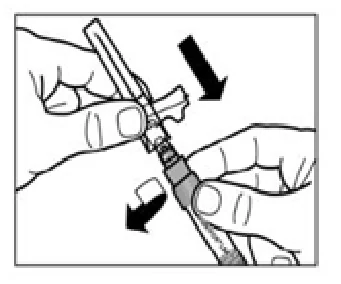 |
Pull the protective cover straight off the needle. To avoid sedimentation, you may gently shake the syringe to maintain a uniform suspension. Gently tap the syringe to remove any visible bubbles and expel them from the syringe. The reconstituted SIGNIFOR LAR is now ready for immediate administration. | 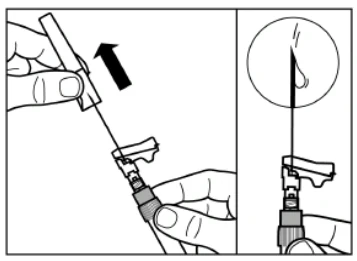 |
Step 8 SIGNIFOR LAR must be given only by deep intramuscular injection; NEVER intravenously. Prepare the injection site with a disinfectant. Insert the needle fully into the left or right gluteus at a 90° angle to the skin. Slowly pull back the plunger to check that no blood vessel has been penetrated (reposition if a blood vessel has been penetrated). Slowly depress the plunger until the syringe is empty. Withdraw the needle from the injection site and activate the safety guard (as shown in Step 9). | Injection Sites 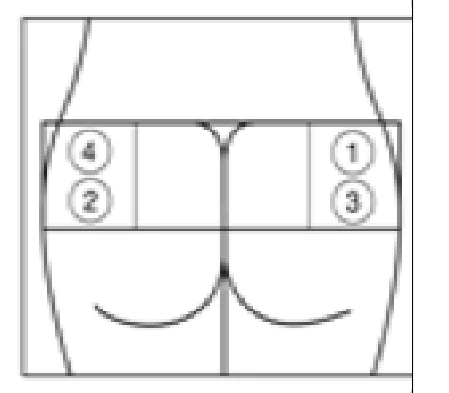 |
Step 9 Activate the safety guard over the needle, in one of the 2 methods shown:
An audible “click” confirms proper activation. Dispose of syringe immediately in a sharps container. | 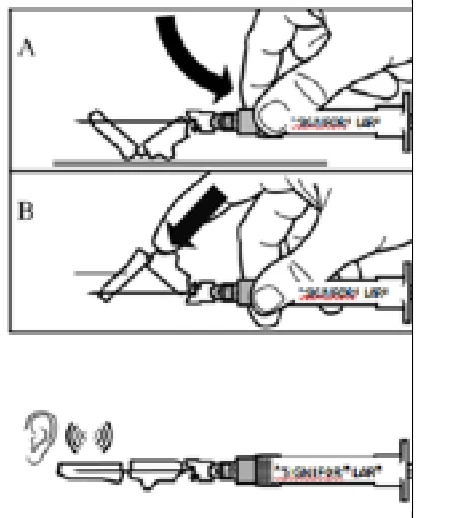 |
Parenteral Products
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL | |||
| 6 mL | 2 mL | 2 mL | 5 mg/mL (10 mg strength) | |||
| 10 mg/mL (20 mg strength) | ||||||
| 15 mg/mL (30 mg strength) | ||||||
| 20 mg/mL (40 mg strength) | ||||||
| 30 mg/mL (60 mg strength) | ||||||
4.4. Administration
SIGNIFOR LAR should only be administered by deep intramuscular injection by a trained health care professional. SIGNIFOR LAR suspension must only be prepared immediately before administration. The site of repeat intramuscular injections should be alternated between the left and right gluteal muscle. Do not use SIGNIFOR LAR if you notice the powder in the vial has changed its color, or the solvent is not clear or contains particles.
4.5. Missed Dose
If a dose of SIGNIFOR LAR is missed, the injection should be administered as soon as possible and next injection should be planned after 4 weeks to reassume normal schedule every 4 weeks.
5. Overdose
In the event of overdosage, it is recommended that appropriate supportive treatment be initiated, as dictated by the patient’s clinical status, until resolution of the symptoms. Electrocardiogram monitoring is recommended.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
6. Dosage Forms, Strengths, Composition and Packaging
Summary of Product Information
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Intramuscular (i.m.) | Powder for Suspension 10 mg, pasireotide (as pamoate) 20 mg, pasireotide (as pamoate) 30 mg, pasireotide (as pamoate) 40 mg, pasireotide (as pamoate) 60 mg, pasireotide (as pamoate) | Vial: Poly (D,L-lactide-co-glycolide) (50-60:40-50), Poly (D,L-lactide-co-glycolide) (50:50). Pre-filled syringe: Carmellose sodium, mannitol, poloxamer 188, water for injections. |
SIGNIFOR LAR is a long-acting depot injection form of pasireotide, powder for suspension for injection to be suspended in a solvent immediately prior to intramuscular (i.m.) injection.
Powder: Slightly yellowish to yellowish powder in vial
Solvent for suspension for injection (solution for reconstitution): clear, colorless to slightly yellow or slightly brown solution in pre-filled syringe
SIGNIFOR LAR is supplied in kits containing:
- One single vial of SIGNIFOR LAR powder (pasireotide for Injectable Suspension) containing 10, 20, 30, 40 or 60 mg of pasireotide (as pamoate) slow release
- One prefilled syringe containing 2 mL of solution for reconstitution
- One vial adapter for drug product reconstitution
- One safety injection needle (20G x 1.5”)
7. Warnings and Precautions
Cardiovascular
Bradycardia and PR Interval Prolongation: Pasireotide causes a decrease in heart rate and PR interval prolongation (see 10.2 Pharmacodynamics – Cardiac Electrophysiology). Careful monitoring of patients with a low heart rate at baseline (<60 beats per minute), a history of syncope or arrhythmia, ischemic heart disease, or congestive heart failure is recommended. Concomitant medications that decrease heart rate, prolong the PR interval and/or prolong the QTc interval should be avoided to the extent possible during treatment with SIGNIFOR LAR (see 9.4 Drug-Drug Interactions).
QTc Prolongation: Pasireotide is associated with QTc prolongation (see 8. Adverse Reactions and 10.2 Pharmacodynamics – Cardiac Electrophysiology). SIGNIFOR LAR should not be used in patients with congenital long QT syndrome (see 2. Contraindications). SIGNIFOR LAR should be used with caution in patients who are at significant risk of developing prolongation of QT, including, but not limited to, the following:
- QTc prolongation at baseline or a family history of sudden cardiac death at <50 years
- with uncontrolled or significant cardiac disease including recent myocardial infarction, congestive heart failure, left ventricular hypertrophy, cardiomyopathy, unstable angina or clinically significant bradycardia, a history of significant arrhythmias, or any other risk factors for torsades de pointes
- taking other substances that are known to lead to QT prolongation, including anti-arrhythmic medicinal products
- diabetes mellitus, especially with autonomic neuropathy
- with hypokalemia, hypocalcaemia and/or hypomagnesaemia (see 7. Warnings and Precautions – Renal)
Female gender and age 65 years or older are risk factors for torsades de pointes.
A baseline ECG is recommended prior to initiating therapy with SIGNIFOR LAR. Monitoring for an effect on the QTc interval is advisable approximately 21 days after initiating therapy and as clinically indicated thereafter. Hypokalemia, hypocalcemia, or hypomagnesemia must be corrected prior to SIGNIFOR LAR administration and should be monitored periodically during therapy (see 7. Warnings and Precautions - Monitoring and Laboratory Tests).
Concomitant medications that cause QTc prolongation should be avoided during treatment with SIGNIFOR LAR (see 9.4 Drug-Drug Interactions). When drugs that prolong the QTc interval are prescribed, healthcare professionals should consider the nature and implications of the ECG changes, underlying diseases and disorders that are considered to represent risk factors, demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug in consultation with the patient.
Driving and Operating Machinery
In clinical trials, adverse drug reactions (ADRs) of dizziness, fatigue, and headache were either very commonly (≥10%) or commonly (≥1%) reported with SIGNIFOR LAR treatment see 8.2 Clinical Trial Adverse Drug Reactions, Acromegaly and Cushing’s disease). Patients should be warned to exercise caution when driving or using machinery if they experience fatigue, headache, or dizziness during treatment with SIGNIFOR LAR.
Endocrine and Metabolism
Glucose metabolism
SIGNIFOR LAR is contraindicated in patients with poor glycemic control (HbA1c values ≥8% while receiving anti-diabetic therapy) (see 2. Contraindications), as they may be at a higher risk of developing severe hyperglycemia and associated complications (e.g. ketoacidosis) (see 8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Glucose metabolism disorders, Acromegaly).
SIGNIFOR LAR can cause increases in blood glucose levels, which are sometimes severe. In pivotal trials, a majority of patients, including those with normal glucose tolerance, pre-diabetes, and diabetes experienced increased glucose levels, and developed pre-diabetes or diabetes when treated with SIGNIFOR LAR (see 8. Adverse Reactions). Based on changes in HbA1c values, in drug-naïve acromegaly patients treated with SIGNIFOR LAR, 77% of patients with normal HbA1c (<5.7) at baseline developed pre-diabetes/diabetes at Month 12, and in acromegaly patients previously treated with somatostatin analogues, 61% and 50% of patients treated with SIGNIFOR LAR 40 mg and 60 mg, respectively, developed pre-diabetes/diabetes at Month 6. The degree and frequency of hyperglycemia observed in the two acromegaly pivotal trials were higher with SIGNIFOR LAR use compared to active control use (octreotide intramuscular or lanreotide subcutaneous injections). Seven acromegaly patients treated with SIGNIFOR LAR were hospitalized for elevated glucose levels; one of whom developed diabetic ketoacidosis (see 8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Glucose metabolism disorders, Acromegaly). In a pooled analysis of the two acromegaly pivotal trials, the overall incidence of hyperglycemia-related adverse reactions was 50.1% (all grades) and 9.1 % (CTC Grade 3 and 4) for SIGNIFOR LAR use versus 13.7% (all grades) and 1.1% (CTC Grade 3 and 4) for the active control. In the pivotal trial in acromegaly patients inadequately controlled on previous treatment with other somatostatin analogues, the proportion of patients not previously treated with antidiabetic agents who required starting of antidiabetic therapy during the trial was 17.5% and 16.1% in the SIGNIFOR LAR 40 mg and 60 mg arms, respectively, compared to 1.5% in the active control arm. In the pivotal trial in drug-naïve acromegaly patients, the proportion of patients who required starting of antidiabetic therapy during the study was 36% in the SIGNIFOR LAR arm compared to 4.4% in the active control arm.
In the Cushing’s disease trial, the prevalence of diabetes increased from 40% at baseline to 56% at Month 12. 44 out of 90 patients (48.9%) with no diabetes at baseline developed hyperglycemia during the trial. There were dose dependent increases in mean fasting plasma glucose (FPG) and HbA1c levels relative to baseline, which occurred early during treatment, continued throughout the duration of the trial, and were greater in patients with diabetes, followed by patients with pre-diabetes, then patients with normal glucose tolerance at baseline. At Month 12, mean percentage (SD) FPG increases from baseline were 33.8% (43.84) in the 10 mg group and 41.3% (49.3) in the 30 mg group, while mean HbA1c levels increased from a baseline value of 5.7% to 6.4% and 6.8% in the 10 mg and 30 mg groups, respectively, (see 8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Glucose metabolism disorders, Cushing's disease). During the trial, the use of antidiabetic agents increased. At baseline, 76% of patients were not on any antidiabetic medication. At Month 12, 70% of patients were on at least one antidiabetic medication. Patients with uncontrolled diabetes were excluded from the trial (see 2. Contraindications). The overall incidence of hyperglycemia related adverse reactions was 76% (all grades), 22.7% (CTC Grade 3), with no Grade 4 adverse reactions reported. Two patients were hospitalized for elevated blood glucose. Adverse reactions of hyperglycemia and diabetes mellitus led to study discontinuation in 3 (2%) and 4 (2.7%) patients, respectively (see 8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Glucose metabolism disorders, Cushing's disease).
There have been post-marketing cases of ketoacidosis in patients taking SIGNIFOR LAR including in patients without a history of diabetes or without other underlying risk factors. In some cases, factors predisposing to ketoacidosis such as acute illness, infection, pancreatic disorders (e.g. pancreatic malignancy or pancreatic surgery), and alcohol abuse were present. Patients who present with signs and symptoms consistent with severe metabolic acidosis should be assessed for ketoacidosis regardless of diabetes history, and Signifor LAR treatment should be stopped with close monitoring of the patient.
Glycemic status (fasting plasma glucose/hemoglobin A1c [FPG/HbA1c]) should be assessed prior to starting treatment with pasireotide. Once SIGNIFOR LAR treatment has been initiated, monitoring of blood glucose should be done weekly for the first three months and at least once monthly after a stable dose of SIGNIFOR LAR has been established. Weekly monitoring should be resumed for three months after a dose increase (see 7. Warnings and Precautions - Monitoring and Laboratory Tests). If uncontrolled hyperglycemia persists, despite appropriate medical management, the dose of SIGNIFOR LAR should be reduced or the treatment with SIGNIFOR LAR should be discontinued. After treatment discontinuation, fasting plasma glucose and hemoglobin A1c should be assessed if indicated. Patients on anti-diabetic therapy discontinuing SIGNIFOR LAR may require more frequent blood glucose monitoring and anti-diabetic drug therapy dose adjustment to mitigate the risk of hypoglycemia.
Hypocortisolism
Suppression of anterior pituitary hormones may occur with SIGNIFOR LAR treatment. The decrease in ACTH (adrenocorticotropic hormone) secretion in acromegaly and Cushing’s disease patients treated with SIGNIFOR LAR can lead to hypocortisolism (see 8. Adverse Reactions). In the Cushing’s disease trial, cases of hypocortisolism-related adverse reactions were reported in 12 (8%) patients, primarily adrenal insufficiency, serious (CTC Grade 3 and 4) adverse events were reported in 3 (2%) patients, and all cases were manageable by reducing the dose of SIGNIFOR LAR and/or adding low-dose, short-term glucocorticoid therapy.
It is therefore necessary to monitor and instruct patients on the signs and symptoms associated with hypocortisolism (e.g. weakness, fatigue, anorexia, nausea, vomiting, hypotension, hyponatremia, or hypoglycemia) (see 7. Warnings and Precautions - Monitoring and Laboratory Tests). In case of documented hypocortisolism, temporary exogenous steroid (glucocorticoid) replacement therapy and/or dose reduction, interruption, or discontinuation of treatment with SIGNIFOR LAR may be necessary (see 4.2 Recommended Dose and Dosage
Adjustment, Cushing’s disease). Rapid decreases in cortisol levels may be associated with decreases in white blood cell count in Cushing’s disease.
Pituitary hormones
Patients might present with deficiency of one or more pituitary hormones. As the pharmacological activity of pasireotide mimics that of somatostatin, inhibition of pituitary hormones, other than GH/IGF-1 in acromegaly patients or ACTH/cortisol in Cushing’s disease patients, cannot be ruled out. Therefore, monitoring of pituitary function (e.g. thyroid; TSH/free T4, adrenal; ACTH/cortisol, gonadal) prior to initiation of therapy with SIGNIFOR LAR and periodically during treatment should be conducted as clinically appropriate (see 7. Warnings and Precautions - Monitoring and Laboratory Tests).
Gastrointestinal
Steatorrhea and Malabsorption of Dietary Fats:
New onset steatorrhea, stool discoloration and loose stools have been reported in patients receiving somatostatin analogs, including pasireotide products. Somatostatin analogs reversibly inhibit secretion of pancreatic enzymes and bile acids, which may result in malabsorption of dietary fats and subsequent symptoms of steatorrhea, loose stools, abdominal bloating, and weight loss. If new occurrence or worsening of these symptoms are reported in patients receiving SIGNIFOR LAR, evaluate patients for potential pancreatic exocrine insufficiency and manage accordingly.
Hematologic
Patients with significantly increased values of prothrombin time (PT) and or partial thromboplastin time (PPT) (elevated by 30% above normal levels), or patients receiving anticoagulants that affect PT or PTT (e.g., coumarin-derivative or heparin-derivative anticoagulants) were excluded from clinical studies with pasireotide. Therefore, the safety of the combination of SIGNIFOR LAR with anticoagulants has not been established (see 9.4 Drug-Drug Interactions). If concomitant use of anticoagulants with SIGNIFOR LAR cannot be avoided, patients should be monitored regularly for alterations in their coagulation parameters and the anticoagulant dose should be adjusted accordingly (see 7. Warnings and Precautions - Monitoring and Laboratory Tests and 9.4 Drug-Drug Interactions).
Hepatic/Biliary/Pancreatic
Hepatic
Increases in liver enzymes have been observed with SIGNIFOR LAR. In the drug-naïve study in acromegaly patients, ALT or AST elevation greater than three times the upper limit of normal (ULN) were observed in 9 patients (5.1%), ALT or AST elevation >5xULN were observed in one patient (0.6%), and total bilirubin elevation ≥2xULN were observed in 4 patients (2.2%) treated with SIGNIFOR LAR. In the trial evaluating patients previously treated with somatostatin analogs, ALT or AST elevations of >3xULN were observed in one patient (1.6%), ALT or AST elevations of >5x ULN were observed in one patient (1.6%), and total bilirubin elevations of ≥2xULN were observed in 2 patients (3.2%) treated with SIGNIFOR LAR 40 mg. Total bilirubin elevations of ≥2xULN were also observed in one patient (1.6%) treated with SIGNIFOR LAR 60 mg. Overall, in both pivotal studies and across all doses, one patient (0.2%) had elevations of ALT or AST >20xULN and 2 patients (0.4%) had elevations of ALT or AST >10xULN. The overall incidence rate of liver safety-related adverse events was 5.3 per 100 PYE.
In the Cushing’s disease trial, hepatic safety results were consistent with those reported in the acromegaly trials. Transient increases in mean ALT and AST values were observed shortly after the initiation of treatment with SIGNIFOR LAR, peaked during the first month of treatment, were less marked in the 10 mg arm compared to the 30 mg arm, and returned to values close to those observed at baseline after Month 3. Mean values remained within normal ranges at all time. Increases in transaminases (ALT or AST >3xULN but ˂5xULN) were reported in 21 (14%) patients, with similar frequencies in both arms (13.5% and 14.5% in the 10 mg and 30 mg arms, respectively). Collectively in both the 10 mg and the 30 mg arms, seven patients (4.7%) had ALT or AST elevations >5xULN but ˂8xULN, one patient in the 30 mg arm (1.3%) had ALT >8xULN, and no patient had ALT or AST elevations >10xULN. In the 30 mg arm, total bilirubin elevations ˃2xULN were reported in two patients (2.6%), one of whom (1.3%) had ˃3xULN elevations. One patient had an increase in ALT/AST >3xULN with concomitant increase in total bilirubin >2xULN and ALP ≤ 2xULN (meeting the biochemical criteria for Hy’s Law, see 3. Serious Warnings and Precautions Box), found only in the context of serious adverse events (SAEs) of cholelithiasis, cholecystitis, and pancreatitis, which recovered after discontinuation of SIGNIFOR LAR. Apart from this patient, no other patient had any grade 4 liver-related adverse events. Liver safety related AEs were reported in 30 (20%) patients, primarily elevated GGT (8.7%) and elevated ALT (7.3%) (see 8.2 Clinical Trial Adverse Drug Reactions, Cushing’s disease). One patient (0.7%) reported a SAE and four patients (2.7%; 2 in each treatment arm) discontinued due to hepatic safety-related adverse events.
Monitoring of liver function is recommended prior to treatment with SIGNIFOR LAR, after the first two to three weeks, at 3 weeks after each dose for the first 3 months on treatment, and then every 3 months thereafter as clinically indicated. Close monitoring should be resumed with any dose increase (see 7. Warnings and Precautions - Monitoring and Laboratory Tests).
Patients who develop increased transaminase levels should be monitored closely until values return to pre-treatment levels. If elevations of ALT exceed 3xULN but are below 5xULN, repeat the test within 48 hours. If values are confirmed below 5xULN, keep on monitoring every 48 hours. If values rise to 5xULN or greater, discontinue SIGNIFOR LAR treatment. SIGNIFOR LAR therapy should be discontinued if elevations of ALT are 5 times the ULN or greater, if sustained elevations of AST occur, if ALT or AST elevations greater than 3 x ULN occur concurrently with bilirubin elevations greater than 2 x ULN, or if the patient develops jaundice or other signs suggestive of clinically significant liver impairment. Following discontinuation of treatment with SIGNIFOR LAR, patients should be monitored until resolution. Treatment should not be restarted. Concomitant medications with hepatotoxic potential should be used with caution during treatment with SIGNIFOR LAR.
Concurrent elevations of ALT or AST >3xULN and total bilirubin ≥2xULN, meeting the definition of Hy’s Law, were reported within 4-10 days of initiating treatment with SIGNIFOR s.c. formulation in 3 healthy volunteers and one Cushing’s disease patient. The cases had an early onset and the patient with Cushing’s disease developed jaundice. Liver test elevations resolved upon discontinuation of SIGNIFOR s.c. One Cushing’s disease patient treated with SIGNIFOR LAR reported concomitant elevations of ALT/AST >3xULN, total bilirubin >2xULN, and ALP ≤ 2xULN (meeting the biochemical criteria for Hy’s Law) in the context of SAEs of cholelithiasis, acute cholecystitis, and edematous pancreatitis (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Glucose metabolism disorders, Liver enzymes).
Biliary
Cholelithiasis (gallstones) have been frequently reported in clinical studies with pasireotide. Cholelithiasis was reported in 33% of drug-naïve and in 10% and 13% of inadequately controlled (40 mg and 60 mg dose, respectively) acromegaly patients treated with SIGNIFOR LAR in acromegaly clinical trials (see 8.2 Clinical Trial Adverse Drug Reactions, Cushing’s disease). Cholelithiasis was reported in 33% of Cushing’s disease patients treated with SIGNIFOR LAR in the Cushing’s disease clinical trial, with an increased frequency in the higher dose group (20% and 45% in the 10 mg and 30 mg dose groups, respectively) (see 8.2 Clinical Trial Adverse Drug Reactions, Cushing’s disease).
There have been post-marketing cases of cholelithiasis in patients taking SIGNIFOR LAR resulting in serious complications including cholecystitis and cholangitis, which have sometimes required cholecystectomy.
Ultrasonic examination of the gallbladder before, and at 6- to 12-month intervals during SIGNIFOR LAR therapy is therefore recommended (see 7. Warnings and Precautions - Monitoring and Laboratory Tests). The presence of gallstones in SIGNIFOR LAR-treated patients is largely asymptomatic; symptomatic stones should be managed according to clinical practice. If complications of cholelithiasis are suspected, discontinue SIGNIFOR LAR and treat appropriately.
Pancreatic
Elevations in lipase and amylase were observed in patients receiving pasireotide in clinical studies and were pronounced in patients with renal impairment (see 7. Warnings and Precautions – Renal). Pancreatitis is a potential adverse reaction associated with the use of SIGNIFOR LAR due to the association between cholelithiasis and acute pancreatitis. Six (4%) patients treated with SIGNIFOR LAR reported pancreatitis-related AEs in the Cushing’s disease trial (2.7% and 5.3% in the 10 mg and 30 mg dose groups, respectively) (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Pancreatic enzymes, Cushing’s disease). The elevations were reversible while continuing treatment (see 7. Warnings and Precautions - Monitoring and Laboratory Tests).
Monitoring and Laboratory Tests
Patients should be evaluated for treatment response after the first month of treatment and periodically thereafter. Patients who do not experience clinical benefit from therapy with SIGNIFOR LAR should be considered for discontinuation (see 4.2 Recommended Dose and Dosage Adjustment, ).
Cyclosporine: Cyclosporine levels should be monitored to maintain therapeutic levels (see 9.4 Drug-Drug Interactions).
Electrocardiograms: A baseline ECG is recommended prior to initiating therapy with SIGNIFOR LAR (see 2. Contraindications). Monitoring for an effect on the QTc interval, heart rate, and AV conduction is advisable approximately 21 days after initiating therapy and periodically thereafter as clinically indicated (see 7. Warning and Precautions - Cardiovascular).
Electrolytes: Hypokalemia, hypocalcaemia, or hypomagnesaemia must be corrected prior to SIGNIFOR LAR administration and should be monitored periodically during therapy (see 7. Warning and Precautions - Cardiovascular and Renal).
Gallbladder Ultrasound: Ultrasonic examination of the gallbladder before, and at 6- to 12-month intervals during SIGNIFOR LAR therapy is recommended (see 7. Warning and Precautions – Hepatic/Biliary/Pancreatic, Biliary).
Glycemic Status: Glycemic status (fasting plasma glucose/hemoglobin A1c [FPG/HbA1c]) should be assessed prior to starting treatment with pasireotide (see 2. Contraindications. Monitoring of blood glucose should be done weekly for the first three months and at least once monthly after a stable dose of SIGNIFOR LAR has been established. Weekly monitoring of blood glucose should be resumed for three months after a dose increase (see 7. Warning and Precautions – Endocrine and Metabolism, Glucose Metabolism).
Hematologic: Regular monitoring of coagulation parameters (PT and PTT) should be performed in patients treated concomitantly with SIGNIFOR LAR and anticoagulant drugs (see 7. Warning and Precautions – Hematologic and 9.4 Drug-Drug Interactions).
Hypocortisolism: It is necessary to monitor and instruct patients on the signs and symptoms associated with hypocortisolism (e.g. weakness, fatigue, anorexia, nausea, vomiting, hypotension, hyponatraemia or hypoglycaemia) (see 7. Warning and Precautions – Hypocortisolism).
Lipase: Lipase should be monitored prior to starting treatment with SIGNIFOR LAR and periodically during treatment especially in patients with severe renal impairment and ESRD (see 7. Warning and Precautions – Hepatic/Biliary/Pancreatic, Pancreatic).
Liver Chemistry: Monitoring of liver chemistry is recommended prior to treatment with SIGNIFOR LAR (see 2. Contraindications). Liver function should be monitored after the first two to three weeks, at 3 weeks after each dose for the first 3 months on treatment, and then every 3 months thereafter as clinically indicated. Close monitoring should be resumed with any dose increase (see 7. Warning and Precautions – Hepatic/Biliary/Pancreatic, Hepatic).
Pituitary Function: Monitoring of pituitary function (e.g. thyroid; TSH/free T4, adrenal; ACTH/cortisol, GH/IGF-1, gonadal) prior to initiation of therapy with SIGNIFOR LAR and periodically during treatment should be conducted as clinically appropriate (see 7. Warning and Precautions – Pituitary hormones).
Renal
Hypokalemia, hypocalcaemia or hypomagnesaemia must be corrected prior to SIGNIFOR LAR administration and electrolytes should be monitored periodically during therapy (see 7. Warnings and Precautions - Monitoring and Laboratory Tests). Caution should be observed in patients with conditions that can lead to electrolyte imbalances (e.g., diarrhea, use of diuretics).
The use of SIGNIFOR LAR with drugs that can disrupt electrolyte levels should be avoided. Such drugs include, but are not limited to, the following: Loop, thiazide, and related diuretics, laxatives and enemas, amphotericin B, and high dose corticosteroids.
In a clinical study of single dose pasireotide s.c. 900 µg, in patients with various degrees of renal impairment, grade 3 and grade 4 increases in amylase, lipase and uric acid and grade 3 decreases in hemoglobin were observed in subjects with severe renal impairment and ESRD. Pasireotide must be used with caution in patients with severe renal impairment and ESRD (see 7. Warnings and Precautions - Monitoring and Laboratory Tests, 4. Dosage and Administration, 10. Clinical Pharmacology).
Reproductive Health:
Fertility
It is unknown whether SIGNIFOR LAR has an effect on human fertility. A reduction in growth hormone (GH) levels and normalisation of insulin-like growth factor 1 (IGF-1) concentration in female acromegalic patients could potentially restore fertility. Similarly, the therapeutic benefits of a reduction or normalization of serum cortisol levels in female patients with Cushing’s disease treated with pasireotide may also lead to improved fertility. Female patients of childbearing potential should be advised to use adequate contraception during treatment with SIGNIFOR LAR (see 7.1.1. Pregnancy). Studies in rats administered pasireotide via the s.c. route have shown effects on female reproductive parameters (see 16. Non-Clinical Toxicology). The clinical relevance of these effects in humans is unknown.
7.1. Special Populations
7.1.1. Pregnancy
Women of child-bearing potential: SIGNIFOR LAR should not be used in women of child-bearing potential who are not using contraception, and for a period of approximately 2-months before conception. Animal studies have shown pasireotide to be harmful to the developing fetus. Women of child-bearing potential are recommended to use effective contraception during treatment with pasireotide (see 7. Warnings and Precautions – Fertility).
Pregnant Women: SIGNIFOR LAR should not be used during pregnancy. There are no adequate and well-controlled studies in pregnant women. Studies in animals administered pasireotide via the s.c. route have shown reproductive toxicity (see 16. Non-Clinical Toxicology). The potential risk for humans is not known.
7.1.2. Breastfeeding
Breast-feeding Women: SIGNIFOR LAR should not be used in breast-feeding women. It is not known whether pasireotide is excreted in human milk. Available data in rats administered pasireotide via the s.c. route have shown excretion of pasireotide in milk (see 16. Non-Clinical Toxicology). A risk to the breast-fed child cannot be excluded.
7.1.3. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. (see 1.1 Pediatrics).
7.1.4. Geriatrics
Geriatrics (≥65 years of age): There are limited data on the use of SIGNIFOR LAR in acromegalic patients and very limited data in Cushing’s disease patients older than 65 years. Clinical studies of SIGNIFOR LAR did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients (see 1.2 Geriatrics).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The safety profile of SIGNIFOR LAR is largely similar between the acromegaly and Cushing’s disease indications.
Acromegaly
A total of 446 acromegaly patients received SIGNIFOR LAR in two pivotal Phase III studies, one in medically naïve patients (N=178) and one in patients inadequately controlled with somatostatin analogues (e.g. octreotide LAR or lanreotide) (N=125). Additional 81 patients randomized and inadequately controlled after 12 months on octreotide LAR in the former study, crossed to pasireotide LAR and were included in the pooled analysis as inadequately controlled patients.
In the pooled data from both pivotal studies, the overall incidence rate (per 100 patient-years exposure, PYE) of adverse drug reactions (ADRs) was 53.2; the most common (incidence rate >10) ADRs were hyperglycemia, cholelithiasis, diarrhea and diabetes mellitus. There were 5 ADRs (per 100 PYE) leading to study discontinuation and 39.2 requiring clinical intervention (dose adjustment/interruption or requiring additional therapy). Hyperglycemia-related (4.0 and 30.6) was the most common ADR leading to discontinuation and requiring clinical intervention, respectively. The overall incidence rate of serious ADRs was 4.1. The most frequent (>0.1) serious ADRs included cholelithiasis, diabetes mellitus, hyperglycemia, cholecystitis and cholecystitis acute. A total of five on-treatment deaths were reported, none suspected to be related to study drug.
Cushing’s disease
The safety data reported below are based on the Phase 3 clinical study G2304 of 150 Cushing’s disease patients, randomized in a 1:1 ratio to receive starting doses of either 10 mg or 30 mg SIGNIFOR LAR every 28 days (q28d), with a possibility to up-titrate to a maximum dose of 40 mg SIGNIFOR LAR q28d after four months of treatment. The following safety analysis is based on data up to a time point when all patients had either completed 12 months of treatment or discontinued. The median duration of exposure was 14.8 months (range 0.9 to 45.8 months) for patients treated with SIGNIFOR LAR at the recommended starting dose of 10 mg q28d, and 12.5 months (range 0.9 to 42.6 months) for patients treated with SIGNIFOR LAR at the starting dose of 30 mg q28d.
The most commonly reported ADRs (incidence ≥20%) were hyperglycemia, diarrhea, cholelithiasis, and diabetes mellitus. The frequency and severity of ADRs tended to be higher in the group starting at the higher dose of 30 mg, but this was not consistent for all ADRs. The most common ADRs requiring dose adjustment (down titration) or temporary interruption were reported in 38 (25%) patients; the most common (incidence ≥2%) were adrenal insufficiency, diabetes mellitus, hyperglycemia, Addison disease, and blood cortisol decreased. Adverse events leading to study discontinuation were reported in 19 (12.7%) patients; the most common (incidence >1%) were diabetes mellitus, hyperglycemia, cholelithiasis, and alanine aminotransferase increased. Serious ADRs were reported in 12 (8%) patients; the most common (incidence >1% in all patients) were cholelithiasis [3 (2%)] and blood cortisol decreased [2 (1.3%)]. Two on-treatment deaths were reported (both in the 30 mg dose group), but none were suspected to be related to study drug.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Acromegaly
Adverse drug reactions reported with a frequency higher than or equal to 1% in the two pivotal clinical trials (Study C2305 and C2402, see 14.1 Clinical Trials by Indication, Acromegaly), are presented below in Table 1 and Table 2 by randomised dose group.
Table 1: Adverse Drug Reactions with a Frequency of Greater than or equal to 1% in the SIGNIFOR LAR 40 mg Group in the Pivotal Phase III Study C2305 in Acromegaly Patients
| Adverse drug reactions | Study C2305 core and extension (mean duration of exposure 75 weeks) in SIGNIFOR LAR group Medically naïve patients | |||||
| SIGNIFOR LAR 40 mg1 n (%) N=178 | SANDOSTATIN® LAR® 20 mg n (%) N=180 | |||||
| Blood and lymphatic system disorders | ||||||
| Microcytic anemia | 3 (1.7) | 3 (1.7) | ||||
| Anemia | 4 (2.2) | 1 (0.6) | ||||
| Cardiac disorders | ||||||
| Sinus bradycardia | 11 (6.2) | 8 (4.4) | ||||
| Bradycardia | 5 (2.8) | 2 (1.1) | ||||
| Atrioventricular block first degree | 3 (1.7) | 2 (1.1) | ||||
| Endocrine disorders | ||||||
| Adrenal insufficiency | 2 (1.1) | 1 (0.6) | ||||
| Gastrointestinal disorders | ||||||
| Diarrhoea | 59 (33.1) | 73 (40.6) | ||||
| Abdominal pain | 23 (12.9) | 32 (17.8) | ||||
| Nausea | 15 (8.4) | 26 (14.4) | ||||
| Abdominal distension | 17 (9.6) | 17 (9.4) | ||||
| Flatulence | 8 (4.5) | 11 (6.1) | ||||
| Vomiting | 7 (3.9) | 10 (5.6) | ||||
| Abdominal pain upper | 7 (3.9) | 9 (5.0) | ||||
| Constipation | 5 (2.8) | 10 (5.6) | ||||
| Dyspepsia | 3 (1.7) | 5 (2.8) | ||||
| Abdominal discomfort | 4 (2.2) | 1 (0.6) | ||||
| Gastrointestinal pain | 4 (2.2) | 1 (0.6) | ||||
| General disorders and administration site conditions | ||||||
| Injection site pain | 13 (7.3) | 9 (5.0) | ||||
| Adverse drug reactions | Study C2305 core and extension (mean duration of exposure 75 weeks) in SIGNIFOR LAR group Medically naïve patients | |||||
| SIGNIFOR LAR 40 mg1 n (%) N=178 | SANDOSTATIN® LAR® 20 mg n (%) N=180 | |||||
| Fatigue | 8 (4.5) | 5 (2.8) | ||||
| Non-cardiac chest pain | 2 (1.1) | 1 (0.6) | ||||
| Hepatobiliary disorders | ||||||
| Cholelithiasis | 55 (30.9) | 66 (36.7) | ||||
| Hepatic steatosis | 6 (3.4) | 6 (3.3) | ||||
| Biliary dilatation | 4 (2.2) | 8 (4.4) | ||||
| Gallbladder polyp | 3 (1.7) | 3 (1.7) | ||||
| Cholecystitis | 3 (1.7) | 2 (1.1) | ||||
| Cholecystitis acute | 2 (1.1) | 1 (0.6) | ||||
| Hepatic cyst | 2 (1.1) | 1 (0.6) | ||||
| Injury, poisoning and procedural complications | ||||||
| Post procedural diarrhoea | 3 (1.7) | 2 (1.1) | ||||
| Investigations | ||||||
| Blood creatine phosphokinase increased | 17 (9.6) | 16 (8.9) | ||||
| Blood glucose increased | 15 (8.4) | 6 (3.3) | ||||
| Alanine aminotransferase increased | 10 (5.6) | 7 (3.9) | ||||
| Lipase increased | 8 (4.5) | 9 (5.0) | ||||
| Glycosylated haemoglobin increased | 10 (5.6) | 4 (2.2) | ||||
| Electrocardiogram QT prolonged | 4 (2.2) | 8 (4.4) | ||||
| Aspartate aminotransferase increased | 7 (3.9) | 5 (2.8) | ||||
| Blood bilirubin increased | 6 (3.4) | 3 (1.7) | ||||
| Weight decreased | 4 (2.2) | 3 (1.7) | ||||
| Blood uric acid increased | 5 (2.8) | 1 (0.6) | ||||
| Blood alkaline phosphatase increased | 2 (1.1) | 4 (2.2) | ||||
| Blood triglycerides increased | 2 (1.1) | 3 (1.7) | ||||
| Adverse drug reactions | Study C2305 core and extension (mean duration of exposure 75 weeks) in SIGNIFOR LAR group Medically naïve patients | |||||
| SIGNIFOR LAR 40 mg1 n (%) N=178 | SANDOSTATIN® LAR® 20 mg n (%) N=180 | |||||
| Blood lactate dehydrogenase increased | 3 (1.7) | 1 (0.6) | ||||
| Blood thyroid stimulating hormone decreased | 2 (1.1) | 1 (0.6) | ||||
| Blood thyroid stimulating hormone increased | 2 (1.1) | 1 (0.6) | ||||
| Bilirubin conjugated increased | 2 (1.1) | 0 | ||||
| Blood amylase increased | 2 (1.1) | 0 | ||||
| Lipids increased | 2 (1.1) | 0 | ||||
| Metabolism and nutrition disorders | ||||||
| Hyperglycaemia | 50 (28.1) | 13 (7.2) | ||||
| Diabetes mellitus | 35 (19.7) | 7 (3.9) | ||||
| Type 2 diabetes mellitus | 11 (6.2) | 0 | ||||
| Decreased appetite | 6 (3.4) | 5 (2.8) | ||||
| Hypoglycaemia | 3 (1.7) | 7 (3.9) | ||||
| Impaired fasting glucose | 6 (3.4) | 0 | ||||
| Glucose tolerance impaired | 3 (1.7) | 1 (0.6) | ||||
| Hyperuricaemia | 3 (1.7) | 0 | ||||
| Hyperlipidemia | 2 (1.1) | 1 (0.6) | ||||
| Hypertriglyceridemia | 2 (1.1) | 1 (0.6) | ||||
| Musculoskeletal and connective tissue disorders | ||||||
| Arthralgia | 2 (1.1) | 5 (2.8) | ||||
| Muscle spasms | 2 (1.1) | 4 (2.2) | ||||
| Back pain | 2 (1.1) | 3 (1.7) | ||||
| Nervous system disorders | ||||||
| Dizziness | 12 (6.7) | 12 (6.7) | ||||
| Headache | 9 (5.1) | 14 (7.8) | ||||
| Adverse drug reactions | Study C2305 core and extension (mean duration of exposure 75 weeks) in SIGNIFOR LAR group Medically naïve patients | ||||||
| SIGNIFOR LAR 40 mg1 n (%) N=178 | SANDOSTATIN® LAR® 20 mg n (%) N=180 | ||||||
| Syncope | 3 (1.7) | 0 | |||||
| Lethargy | 2 (1.1) | 0 | |||||
| Skin and subcutaneous tissue disorders | |||||||
| Alopecia | 28 (15.7) | 26 (14.4) | |||||
| Dry skin | 2 (1.1) | 0 | |||||
| Pruritus | 2 (1.1) | 0 | |||||
| Vascular disorders | |||||||
| Hypertension | 3 (1.7) | 2 (1.1) | |||||
| 1 Dose increase to 60 mg of SIGNIFOR LAR and dose increase to 30 mg of SANDOSTATIN® LAR® were permitted after the first three or six months of treatment (steady-state reached) if biochemical parameters showed a mean GH ≥2.5 microgram/L and/or IGF-1 >ULN (age and sex related). | |||||||
Table 2: Adverse Drug Reactions with a Frequency of Greater than or equal to 1% in the SIGNIFOR LAR 40 mg or 60 mg Groups in the Pivotal Phase III Study C2402 in Acromegaly Patients
| Adverse drug reactions | Study C2402 core (mean duration of exposure 24 weeks) Inadequately controlled patients | ||||||
| SIGNIFOR LAR 40 mg n (%) N=63 | SIGNIFOR LAR 60 mg n (%) N=62 | Active Control n (%) N=66 | |||||
| Blood and lymphatic system disorders | |||||||
| Anemia | 2 (3.2) | 0 | 0 | ||||
| Endocrine disorders | |||||||
| Adrenal insufficiency | 1 (1.6) | 0 | 0 | ||||
| Eye disorders | |||||||
| Adverse drug reactions | Study C2402 core (mean duration of exposure 24 weeks) Inadequately controlled patients | |||||||||||
| SIGNIFOR LAR 40 mg n (%) N=63 | SIGNIFOR LAR 60 mg n (%) N=62 | Active Control n (%) N=66 | ||||||||||
| Eye irritation | 0 | 1 (1.6) | 0 | |||||||||
| Gastrointestinal disorders | ||||||||||||
| Diarrhoea | 7 (11.1) | 12 (19.4) | 1 (1.5) | |||||||||
| Abdominal pain | 4 (6.3) | 3 (4.8) | 0 | |||||||||
| Nausea | 1(1.6) | 2 (3.2) | 0 | |||||||||
| Dyspepsia | 0 | 1 (1.6) | 0 | |||||||||
| Tongue coated | 0 | 1 (1.6) | 0 | |||||||||
| Abdominal distension | 1 (1.6) | 0 | 1 (1.5) | |||||||||
| Abdominal pain upper | 1 (1.6) | 0 | 0 | |||||||||
| Constipation | 2 (3.2) | 0 | 0 | |||||||||
| Flatulence | 3 (4.8) | 0 | 1 (1.5) | |||||||||
| Gastrointestinal pain | 1 (1.6) | 0 | 0 | |||||||||
| Vomiting | 1 (1.6) | 0 | 0 | |||||||||
| General disorders and administration site conditions | ||||||||||||
| Asthenia | 0 | 2 (3.2) | 0 | |||||||||
| Fatigue | 1 (1.6) | 2 (3.2) | 0 | |||||||||
| Gait disturbance | 0 | 1 (1.6) | 0 | |||||||||
| Injection site pain | 0 | 1 (1.6) | 2 (3.0) | |||||||||
| Hepatobiliary disorders | ||||||||||||
| Cholelithiasis | 6 (9.5) | 7 (11.3) | 8 (12.1) | |||||||||
| Biliary colic | 1 (1.6) | 0 | 0 | |||||||||
| Liver injury | 1 (1.6) | 0 | 0 | |||||||||
| Infections and infestations | ||||||||||||
| Pharyngitis | 1 (1.6) | 0 | 0 | |||||||||
| Vulval cellulitis | 1 (1.6) | 0 | 0 | |||||||||
| Injury, poisoning and procedural complications | ||||||||||||
| Wound | 0 | 1 (1.6) | 0 | |||||||||
| Sunburn | 1 (1.6) | 0 | 0 | |||||||||
| Adverse drug reactions | Study C2402 core (mean duration of exposure 24 weeks) Inadequately controlled patients | |||||||||||
| SIGNIFOR LAR 40 mg n (%) N=63 | SIGNIFOR LAR 60 mg n (%) N=62 | Active Control n (%) N=66 | ||||||||||
| Investigations | ||||||||||||
| Blood glucose increased | 3 (4.8) | 4 (6.5) | 0 | |||||||||
| Glycosylated haemoglobin increased | 0 | 2 (3.2) | 0 | |||||||||
| Alanine aminotransferase increased | 0 | 1 (1.6) | 0 | |||||||||
| Blood albumin decreased | 0 | 1 (1.6) | 0 | |||||||||
| Blood alkaline phosphatase increased | 0 | 1 (1.6) | 0 | |||||||||
| Blood creatinine increased | 0 | 1 (1.6) | 0 | |||||||||
| Blood urea increased | 0 | 1 (1.6) | 0 | |||||||||
| Blood uric acid increased | 0 | 1 (1.6) | 0 | |||||||||
| Gamma-glutamyltransferase increased | 0 | 1 (1.6) | 1 (1.5) | |||||||||
| Glucose urine present | 0 | 1 (1.6) | 0 | |||||||||
| Weight decreased | 0 | 1 (1.6) | 0 | |||||||||
| Blood magnesium decreased | 1 (1.6) | 0 | 0 | |||||||||
| Glucose tolerance decreased | 1 (1.6) | 0 | 0 | |||||||||
| Metabolism and nutrition disorders | ||||||||||||
| Hyperglycaemia | 21 (33.3) | 18 (29.0) | 4 (6.1) | |||||||||
| Diabetes mellitus | 12 (19.0) | 16 (25.8) | 3 (4.5) | |||||||||
| Glucose tolerance impaired | 1 (1.6) | 3 (4.8) | 3 (4.5) | |||||||||
| Type 2 diabetes mellitus | 0 | 2 (3.2) | 1 (1.5) | |||||||||
| Carbohydrate intolerance | 0 | 1 (1.6) | 0 | |||||||||
| Diabetes mellitus inadequate control | 0 | 1 (1.6) | 0 | |||||||||
| Impaired fasting glucose | 1 (1.6) | 0 | 0 | |||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||
| Arthralgia | 0 | 1 (1.6) | 0 | |||||||||
| Muscle spasms | 1 (1.6) | 0 | 0 | |||||||||
| Adverse drug reactions | Study C2402 core (mean duration of exposure 24 weeks) Inadequately controlled patients | ||||||||
| SIGNIFOR LAR 40 mg n (%) N=63 | SIGNIFOR LAR 60 mg n (%) N=62 | Active Control n (%) N=66 | |||||||
| Nervous system disorders | |||||||||
| Dizziness | 4 (6.3) | 1 (1.6) | 0 | ||||||
| Headache | 1 (1.6) | 1 (1.6) | 0 | ||||||
| Psychiatric disorders | |||||||||
| Restlessness | 0 | 1 (1.6) | 0 | ||||||
| Affective disorder | 1 (1.6) | 0 | 0 | ||||||
| Reproductive system and breast disorders | |||||||||
| Erectile dysfunction | 0 | 1 (1.6) | 0 | ||||||
| Menstruation irregular | 1 (1.6) | 0 | 0 | ||||||
| Skin and subcutaneous tissue disorders | |||||||||
| Alopecia | 1 (1.6) | 4 (6.5) | 0 | ||||||
| Vascular disorders | |||||||||
| Hot flush | 0 | 1 (1.6) | 0 | ||||||
| Hypertension | 0 | 1 (1.6) | 0 | ||||||
Cushing's disease
Adverse drug reactions reported with a frequency higher than or equal to 2% (in either the 10 mg or the 30 mg dose groups) in the Cushing’s disease pivotal clinical trial (Study G2304, see 14.1 Clinical Trials by Indication, Cushing's disease) are presented in Table 3 below by randomized dose group.
Table 3: Adverse Drug Reactions With a Frequency of ≥ 2% in the SIGNIFOR LAR 10 mg or 30 mg Dose Groups in the Phase 3 Study G2304 in Cushing’s Disease Patients
| Adverse drug reactions | Study G2304 (mean duration of exposure 68 weeks) | ||||||||||
| Primary System Organ Class Preferred Term | SIGNIFOR LAR 10 mg n (%) N=74 | SIGNIFOR LAR 30 mg n (%) N=76 | Overall n (%) N=150 | ||||||||
| Blood and lymphatic system disorders | |||||||||||
| Anemia | 0 | 4 (5.3) | 4 (2.7) | ||||||||
| Cardiac Disorders | |||||||||||
| Sinus bradycardia1 | 3 (4.1) | 4 (5.3) | 7 (4.7) | ||||||||
| Ear and Labyrinth disorders | |||||||||||
| Vertigo | 2 (2.7) | 0 | 2 (1.3) | ||||||||
| Endocrine disorders | |||||||||||
| Adrenal insufficiency | 3 (4.1) | 5 (6.6) | 8 (5.3) | ||||||||
| Addison’s disease | 2 (2.7) | 3 (3.9) | 5 (3.3) | ||||||||
| Gastrointestinal disorders | |||||||||||
| Diarrhea | 21 (28.4) | 27 (35.5) | 48 (32.0) | ||||||||
| Abdominal pain2 | 13 (17.6) | 16 (21.1) | 29 (19.3) | ||||||||
| Nausea | 11 (14.9) | 11 (14.5) | 22 (14.7) | ||||||||
| Constipation | 4 (5.4) | 1 (1.3) | 5 (3.3) | ||||||||
| Flatulence | 3 (4.1) | 2 (2.6) | 5 (3.3) | ||||||||
| Vomiting | 3 (4.1) | 1 (1.3) | 4 (2.7) | ||||||||
| Frequent bowel movement | 2 (2.7) | 0 | 2 (1.3) | ||||||||
| General disorders and administration site conditions | |||||||||||
| Fatigue3 | 13 (17.6) | 8 (10.5) | 21 (14.0) | ||||||||
| Hepatobiliary disorders | |||||||||||
| Cholelithiasis | 14 (18.9) | 33 (43.4) | 47 (31.3) | ||||||||
| Cholestasis | 4 (5.4) | 2 (2.6) | 6 (4.0) | ||||||||
| Gallbladder cholesterolosis | 2 (2.7) | 4 (5.3) | 6 (4.0) | ||||||||
| Liver injury | 2 (2.7) | 2 (2.6) | 4 (2.7) | ||||||||
| Biliary colic | 0 | 2 (2.6) | 2 (1.3) | ||||||||
| Gallbladder disorder | 0 | 2 (2.6) | 2 (1.3) | ||||||||
| Hepatic function abnormal | 0 | 2 (2.6) | 2 (1.3) | ||||||||
| Adverse drug reactions | Study G2304 (mean duration of exposure 68 weeks) | ||||||||||
| Primary System Organ Class Preferred Term | SIGNIFOR LAR 10 mg n (%) N=74 | SIGNIFOR LAR 30 mg n (%) N=76 | Overall n (%) N=150 | ||||||||
| Investigations | |||||||||||
| Blood glucose increased | 6 (8.1) | 7 (9.2) | 13 (8.7) | ||||||||
| Gamma-glutamyltransferase increased | 7 (9.5) | 3 (3.9) | 10 (6.7) | ||||||||
| Alanine aminotransferase increased | 5 (6.8) | 3 (3.9) | 8 (5.3) | ||||||||
| Glycosylated hemoglobin increased | 4 (5.4) | 4 (5.3) | 8 (5.3) | ||||||||
| Aspartate aminotransferase increased | 3 (4.1) | 1 (1.3) | 4 (2.7) | ||||||||
| Blood cortisol decreased | 2 (2.7) | 2 (2.6) | 4 (2.7) | ||||||||
| Lipase increased | 0 | 4 (5.3) | 4 (2.7) | ||||||||
| Blood creatinine phosphokinase increased | 1 (1.4) | 2 (2.6) | 3 (2.0) | ||||||||
| Insulin-like growth factor decreased | 2 (2.7) | 0 (0.0) | 2 (1.3) | ||||||||
| Metabolism and nutrition disorders | |||||||||||
| Hyperglycemia | 35 (47.3) | 35 (46.1) | 70 (46.7) | ||||||||
| Diabetes mellitus4 | 16 (21.6) | 22 (28.9) | 38 (25.3) | ||||||||
| Decreased appetite | 2 (2.7) | 8 (10.5) | 10 (6.7) | ||||||||
| Glucose tolerance impaired | 2 (2.7) | 3 (3.9) | 5 (3.3) | ||||||||
| Hypoglycemia | 2 (2.7) | 2 (2.6) | 4 (2.7) | ||||||||
| Hypercholesterolemia | 1 (1.4) | 2 (2.6) | 3 (2.0) | ||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||
| Back pain | 2 (2.7) | 1 (1.3) | 3 (2.0) | ||||||||
| Nervous system disorders | |||||||||||
| Dizziness | 5 (6.8) | 0 | 5 (3.3) | ||||||||
| Headache | 2 (2.7) | 3 (3.9) | 5 (3.3) | ||||||||
| Dysgeusia | 2 (2.7) | 1 (1.3) | 3 (2.0) | ||||||||
| Psychiatric disorders | |||||||||||
| Insomnia | 2 (2.7) | 0 | 2 (1.3) | ||||||||
| Adverse drug reactions | Study G2304 (mean duration of exposure 68 weeks) | ||||||
| Primary System Organ Class Preferred Term | SIGNIFOR LAR 10 mg n (%) N=74 | SIGNIFOR LAR 30 mg n (%) N=76 | Overall n (%) N=150 | ||||
| Skin and subcutaneous tissue disorders | |||||||
| Skin exfoliation | 2 (2.7) | 4 (5.3) | 6 (4.0) | ||||
| Pruritus | 1 (1.4) | 3 (3.9) | 4 (2.7) | ||||
| Alopecia | 0 | 3 (3.9) | 3 (2.0) | ||||
| Dry skin | 0 | 2 (2.6) | 2 (1.3) | ||||
| Vascular disorders | |||||||
| Hypertension | 2 (2.7) | 2 (2.6) | 4 (2.7) | ||||
1 Sinus bradycardia consists of the two preferred terms: Sinus bradycardia and bradycardia 2 Abdominal pain consists of the four preferred terms: Abdominal pain, abdominal distension, abdominal discomfort, and abdominal pain upper 3 Fatigue consists of the two preferred terms: Fatigue and asthenia 4 Diabetes mellitus consists of the two preferred terms: Diabetes mellitus and type 2 diabetes mellitus | |||||||
8.3. Less Common Clinical Trial Adverse Reactions
Acromegaly
All ADRs which occurred in the two Phase III studies with a frequency less than 1% were:
Cardiac disorders: Angina pectoris, conduction disorder, palpitations, supraventricular extrasystoles
Ear and labyrinth disorders: Hypoacusis
Endocrine disorders: Growth hormone deficiency, hypothyroidism
Eye disorders: Vision blurred
Gastrointestinal disorders: Dry mouth, frequent bowel movements, gastritis, haematochezia, pancreatic disorder, pancreatitis, steatorrhea, teeth brittle
General disorders and administration site conditions: Concomitant disease progression, induration, injection site mass, injection site nodule, malaise, oedema peripheral, thirst
Hepatobiliary disorders: Bile duct stone, biliary colic, deficiency of bile secretion, gallbladder disorder, gallbladder enlargement, hepatomegaly, hyperbilirubinaemia
Infections and infestations: Injection site abscess
Injury, poisoning and procedural complications: Procedural nausea
Investigations: Blood calcium increased, blood cholesterol increased, blood cortisol decreased, blood magnesium decreased, blood magnesium increased, blood sodium decreased, blood urea increased, blood uric acid decreased, electrocardiogram ST segment depression, electrocardiogram T wave amplitude decreased, electrocardiogram T wave biphasic, electrocardiogram T wave inversion, high density lipoprotein decreased, insulin-like growth factor decreased, liver scan abnormal, low density lipoprotein decreased, low density lipoprotein increased, protein total decreased, transaminases increased
Metabolism and nutrition disorders: Cholesterosis, hypercholesterolemia, hyperkalemia, hypoalbuminaemia, hypokalemia, hypomagnesaemia, hypophosphatemia, lack of satiety
Musculoskeletal and connective tissue disorders: Hypercreatinaemia, muscular weakness, musculoskeletal pain, myalgia, myositis, pain in extremity
Neoplasms benign, malignant and unspecified: Haemangioma
Nervous system disorders: Diabetic hyperglycaemic coma, disturbance in attention, somnolence
Psychiatric disorders: Depressed mood, insomnia
Renal and urinary disorders: Haematuria, nephropathy
Reproductive system and breast disorders: Benign prostatic hyperplasia, vaginal haemorrhage
Respiratory, thoracic and mediastinal disorders: Cough, hiccups
Skin and subcutaneous tissue disorders: Hyperhidrosis, rash generalised, rosacea, urticaria
Vascular disorders: Flushing
Cushing's Disease
The ADRs which occurred in the Cushing’s disease phase 3 Study G2304 with a frequency of ≥1% and <2% (in either the 10 mg or the 30 mg dose groups) were:
Cardiac disorders: Palpitations, arrhythmia supraventricular, atrioventricular block first degree, supraventricular extrasystoles
Endocrine disorders: Growth hormone deficiency, hyperadrenocorticism, hypercorticoidism, hypothyroidism
Eye disorders: Vision blurred
Gastrointestinal disorders: Breath odour, abnormal feces, ascites, defecation urgency, dry mouth, feces pale, hemorrhoids, edematous pancreatitis
General disorders and administration site conditions: Microlithiasis, edema peripheral, pain, discomfort, injection site hypersensitivity, injection site pain, malaise
Hepatobiliary disorders: Gall bladder polyp, biliary cyst, biliary dilatation, biliary tract disorder, cholecystitis, cholecystitis acute, cholecystitis chronic, gallbladder enlargement, hepatic steatosis
Infection and infestations: Gastroenteritis
Injury, poisoning, and procedural complications: Radius fracture
Investigations: Blood bilirubin increased, blood insulin decreased, hepatic enzyme increased, liver function test abnormal, amylase increased, blood corticotrophin decreased, blood glucose fluctuations, blood sodium increased, blood urea increased, electrocardiogram QT prolonged, electrocardiogram T wave amplitude decreased, electrocardiogram repolarization abnormality, hepatic enzyme abnormal, prothrombin time prolonged, transaminases increased, urine leukocyte esterase positive, weight increased
Metabolism and nutrition disorders: Increased appetite, dehydration, hyperkalemia, hyperuricemia, hypomagnesemia, hyponatremia, impaired fasting glucose, type I diabetes mellitus
Musculoskeletal and connective tissue disorders: Arthralgia, joint swelling, muscular weakness, musculoskeletal chest pain, myalgia, neck pain, pain in extremity
Nervous system disorders: Dizziness postural, memory impairment, somnolence
Psychiatric disorders: Irritability, anxiety, depressed mood, sleep disorder
Renal and urinary disorders: Acute kidney injury, nocturia, proteinuria, urinary incontinence.
Reproductive system and breast disorders: Menorrhagia
Respiratory, thoracic, and mediastinal disorders: Epistaxis
Skin and subcutaneous tissue disorders: Erythema
Vascular disorders: Deep vein thrombosis, hypotension, orthostatic hypotension
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Liver enzymes
Elevations in liver enzymes have been reported in healthy subjects and in patients receiving pasireotide in clinical studies. Overall, in pivotal studies with SIGNIFOR LAR across all doses, one patient (0.2%) had elevations of ALT or AST >20xULN, 2 patients (0.3%) had elevations of ALT or AST >10xULN, one patient (0.2%) had elevations of ALT >8xULN, 11 patients (2%) had elevations of ALT or AST >5xULN, and 33 patients (6%) had elevations of ALT or AST >3xULN. Elevations in total bilirubin ≥2xULN were observed in 11 patients (2%).
Four cases of concurrent elevations in ALT greater than 3xULN and bilirubin greater than 2xULN have been observed with the paseriotide subcutaneous formulation. All cases of concurrent elevations were identified within ten days of initiation of treatment. Liver function test results returned to baseline values after discontinuation of treatment. One Cushing’s disease patient treated with SIGNIFOR LAR reported concomitant elevations of ALT/AST >3xULN, total bilirubin >2xULN, and ALP ≤ 2xULN in the context of SAEs of cholelithiasis, acute cholecystitis, and edematous pancreatitis. Grade 4 elevations of hepatic enzymes were reported on Day 500 of Study G2304. The treatment was discontinued, the patient underwent cholecystectomy, and the SAEs were resolved, with no liver enzyme values reported following discontinuation (see 2. Contraindications, 7 Warning and Precautions – Hepatic/Biliary/Pancreatic, Hepatic and Monitoring and Laboratory Tests).
Glucose metabolism disorders
Acromegaly
Elevated fasting plasma glucose (FPG) was the most frequently reported CTC grade 3/4 laboratory abnormality in both acromegaly phase 3 studies. In Study C2305, grade 3 elevated FPG levels (13.9 – 27.8 mmol/L) were reported in 9.7% and 0.6% and grade 4 FPG levels (>27.8 mmol/L) were reported in 0.6% and 0% of acromegaly patients treated with SIGNIFOR LAR and the active control, respectively. In the core and extension phases, adverse reactions of diabetes mellitus and hyperglycemia led to study discontinuation in 3 (1.7%) versus 2 (1.1%) patients and in 2 (1.1%) vs. 0% patients in the SIGNIFOR LAR and the active control arms, respectively. In Study C2402, grade 3 elevated FPG levels (13.9 – 27.8 mmol/L) were reported in 14.3% and 17.7% of patients in the SIGNIFOR LAR 40 mg and 60 mg groups, respectively, and none in the active control group. Hyperglycemia related adverse reactions led to study discontinuation in 6 (4.8%) patients in the SIGNIFOR LAR arms only; 2 (3.2%) patients in 40 mg arm and 4 (6.5%) patients in 60 mg arm.
In Study C2305, five acromegaly patients naïve to drug therapy exposed to SIGNIFOR LAR (two of whom were normoglycemic at baseline) were hospitalized for blood glucose in the range of 19.82-28.08 mmol/L and none in the active comparator group. Two additional acromegaly patients, who had received active comparator in the main trial and were switched to SIGNIFOR LAR in the extension trial, were hospitalized for elevated glucose levels while on SIGNIFOR LAR treatment during the extension; one of those patients developed diabetic ketoacidosis.
In both studies, mean FPG and HbA1c levels peaked within the first 3 months of treatment with SIGNIFOR LAR. The elevations of FPG and HbA1c observed with SIGNIFOR LAR treatment were reversible after discontinuation.
Cushing’s disease
Elevated FPG was the most frequently reported CTC grade 3 laboratory abnormality (14.7% of patients) in the phase 3 Study G2304 in Cushing’s disease patients; with no cases of grade 4. Mean HbA1c increases were less pronounced in patients who were normoglycemic at study entry in comparison to pre-diabetic patients or diabetic patients (Table 4).
Table 4: Changes in Mean HbA1c (±SD) at Month 12 According to Glycemic Status at Study Entry (Study G2304)
| Glycemic Status at Study Entry n=Number of Patients | 10 mg Q28 days | 30 mg Q28 days | ||||||||
| Baseline | Month 12 | Baseline | Month 12 | |||||||
| Normoglycemic patients | 5.3±0.28 | 6.4±1.31 | 5.1±0.29 | 6.5±1.07 | ||||||
| (n=35) | (n=22) | (n=31) | (n=23) | |||||||
| Pre-diabetic patients | 5.8±0.33 | 6.9±1.14 | 5.7±0.25 | 7.1±1.54 | ||||||
| (n=12) | (n=8) | (n=12) | (n=9) | |||||||
| Diabetic patients | 6.1±0.67 | 7.4±1.40 | 6.2±0.69 | 7.6±1.41 | ||||||
| (n=27) | (n=18) | (n=33) | (n=21) | |||||||
Mean FPG levels commonly increased within the first month of treatment with decreases and stabilization observed in subsequent months, but levels remained elevated above baseline values throughout the duration of the study. Mean FPG levels were 125.6 mg/dL in the 10 mg and 128.7 mg/dL in the 30 mg arm at Month 12. Mean HbA1c levels increased at Month 2 and remained relatively stable thereafter. FPG and HbA1c increases were dose-dependent, and values generally decreased following SIGNIFOR LAR discontinuation but remained above baseline values. Adverse reactions of diabetes mellitus and hyperglycemia led to study discontinuation in 3 (2.0%) and 4 patients (2.7%), respectively. Two patients were hospitalized for elevated blood glucose levels below 500 mg/dL, and no patient developed diabetic ketoacidosis. These two patients discontinued treatment due to SAEs of hyperglycemia and exacerbation of diabetes, respectively.
Monitoring of blood glucose levels in patients is required prior to and during treatment with SIGNIFOR LAR (see 2. Contraindications, 7. Warnings and Precautions, and 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
Pancreatic enzymes
Acromegaly
In the drug-naïve Study C2305, asymptomatic elevations in lipase and alpha amylase were observed in 31% and 24% of patients. In Study C2402 evaluating patients previously treated with somatostatin analogs, asymptomatic elevations in alpha amylase were reported in 10% in the 40 mg arm and in 5% in the 60 mg arm. Asymptomatic elevations in lipase were reported only in the 40 mg arm in 2% of patients. The overall incidence rate of pancreatitis-related adverse events was 5.9 per 100 PYE in both phase 3 studies and across all doses.
Cushing’s disease
In the Cushing’s disease Study G2304, elevations in lipase and amylase (all grades) were reported in 6 (4%) and 1 (0.7%) patients, respectively. Grade 3 elevations in lipase were reported in 3 (2%) patients (2 (2.7%) and 1 (1.3%) in the 10 mg and 30 mg dose groups, respectively), and grade 3 elevations in amylase were reported in 1 (0.7%) patient in the 30 mg group. There were no grade 4 events reported. These laboratory abnormalities were reported as pancreatitis-related adverse events in a total 6 (4%) patients (2 (2.7%) and 4 (5.3%) in the 10 mg and 30 mg dose groups, respectively) (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
Pancreatitis is a potential adverse reaction associated with the use of somatostatin analogs due to the association between cholelithiasis and acute pancreatitis.
QT prolongation
Acromegaly
In the two phase 3 acromegaly trials, a corrected QT interval (i.e., QTcF) of greater than 480 ms was reported in four patients administered SIGNIFOR LAR (3 patients in Study C2305 and one patient in Study C2402 in the 40 mg group) and an increase in the QTcF from baseline of greater than 60 ms was reported for two patients taking SIGNIFOR LAR in Study C2305 (see 8.2 Clinical Trial Adverse Drug Reactions, Acromegaly and 14.1 Clinical Trials by Indication, Acromegaly).
Cushing’s disease
In Study G2304 in Cushing’s disease, 2 (1.3%) patients experienced a QTcF value >480 ms and an increase in the QTcF from baseline of ˃60 ms was reported for 5 (3.3%) patients administered SIGNIFOR LAR (see 8.2. Clinical Trial Adverse Drug Reactions, Cushing’s disease and 14.1 Clinical Trials by Indication, Cushing's disease).
No patient administered SIGNIFOR LAR had a QTcF value of >500 ms in any of the pivotal clinical studies.
8.5. Post-Market Adverse Reactions
The following adverse drug reactions have been derived from post-marketing experience with SIGNIFOR LAR. Because these reactions were reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency
Metabolism and nutrition disorders: Diabetic ketoacidosis.
Hepatobiliary Disorders: Cholangitis
Gastrointestinal Disorders: Malabsorption of dietary fat, Steatorrhea, Feces discolored including Feces pale
9. Drug Interactions
9.2. Drug Interactions Overview
Caution is required when co-administering SIGNIFOR LAR with drugs that are known to have hepatotoxic potential, or with anti-arrhythmic medicines and other drugs that may prolong the QT interval (see 7. Warnings and Precautions). Medications that may disrupt electrolyte levels should be avoided when using SIGNIFOR LAR.
In vitro assessment of drug interactions:
Pasireotide appears to be a substrate of efflux transporter P-gp (P-glycoprotein), but is not an inducer of P-gp. In addition, at therapeutic dose levels, pasireotide is not expected to be:
- A substrate of the efflux transporter BCRP (breast cancer resistance protein) nor of the influx transporters OCT1 (organic cation transporter 1) and OATP (organic anion-transporting polypeptide) 1B1, 1B3 or 2B1;
- An inhibitor of UGT1A1 (uridine diphosphate glucuronosyltransferase 1A1), influx transporter OAT1 or OAT3, OATP 1B1 or 1B3, and OCT1 or OCT2, efflux transporter P-gp, BCRP, MRP2 (multi-drug resistance protein 2) or BSEP (bile salt export pump).
9.3. Drug-Behavioural Interactions
Patients should be warned to exercise caution when driving or using machinery if they experience fatigue, headache, or dizziness during treatment with SIGNIFOR LAR.
The interaction of SIGNIFOR LAR with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4. Drug-Drug Interactions
No clinical drug-drug interaction studies have been performed with SIGNIFOR LAR.
General: The lists below of potentially interacting drugs are not comprehensive. Current information sources should be consulted for newly approved drugs that prolong the QTc interval, decrease heart rate, prolong the PR interval, or cause electrolyte disturbances, as well as for older drugs for which these effects have recently been established.
Effect of Other Drugs on SIGNIFOR LAR
QTc-Prolonging Drugs: The concomitant use of SIGNIFOR LAR with another QTc-prolonging drug should be avoided (see 7. Warnings and Precautions – Cardiovascular and Monitoring and Laboratory Tests; 8. Adverse Reactions and 10.2 Pharmacodynamics – Cardiac Electrophysiology). Drugs that have been associated with QTc interval prolongation and/or torsades de pointes include, but are not limited to, the examples in the following list. Chemical/ pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QTc prolongation and/or torsades de pointes:
- Class IA, III, and 1C antiarrhythmics
- antipsychotics
- antidepressants
- opioids
- macrolide antibiotics and analogues
- quinolone antibiotics
- antimalarials
- azole antifungals
- dopamine receptor antagonists
- serotonin 5-hydroxytryptamine (5-HT3) receptor antagonists
- tyrosine kinase inhibitors
- histone deacetylase inhibitors
- beta-2 adrenoceptor agonists
Drugs that Decrease Heart Rate and/or Prolong the PR Interval: SIGNIFOR LAR results in a decrease in heart rate and an increase in the PR interval (see 7. Warnings and Precautions – Cardiovascular and Monitoring and Laboratory Tests and 10.2 Pharmacodynamics – Cardiac Electrophysiology). The concomitant use of SIGNIFOR LAR with other drugs that lower heart rate and/or prolong the PR interval, including, but not limited to, antiarrhythmics, beta blockers, non-dihydropyridine calcium channel blockers, digitalis glycosides, alpha2-adrenoceptor agonists, cholinesterase inhibitors, sphingosine-1 phosphate receptor modulators, and HIV protease inhibitors, should be avoided.
P-gp Substrate Interactions: Pasireotide appears to be a substrate of efflux transporter P-gp (P-glycoprotein) but is not an inducer of P-gp.
The influence of a P-gp inhibitor on the pharmacokinetics of subcutaneous pasireotide (600 μg, single dose) was tested in a drug-drug interaction study with co-administration of verapamil sustained release formulation (SR) (240 mg, multiple dose) in healthy volunteers. No change in the rate of pasireotide absorption and elimination or extent of exposure following concomitant administration with verapamil SR was observed. However, grade 3 neutropenia, grade 3 lymphopenia, as well as grade 4 lipase and creatine phosphokinase (CPK) increase were observed in some subjects on co-administration. Co-administration of pasireotide with non-dihydropyridine calcium channel blockers such as verapamil should be avoided because of the risk of pharmacodynamic interactions affecting atrioventricular conduction.
The potential for other strong P-gp inhibitors such as ketoconazole, cyclosporine, clarithromycin, to increase concentrations of pasireotide is unknown.
Effect of SIGNIFOR LAR on Other Drugs
The use of SIGNIFOR LAR with drugs that can disrupt electrolyte levels should be avoided. Such drugs include, but are not limited to loop, thiazide, and related diuretics; laxatives and enemas; amphotericin B; and high dose corticosteroids.
Anticoagulants: The safety of the combination of SIGNIFOR LAR with anticoagulants has not been established. If concomitant use of anticoagulants with SIGNIFOR LAR cannot be avoided, coagulation parameters should be monitored regularly and the anticoagulant dose should be revised accordingly (see 7. Warnings and Precautions - Hematologic and Monitoring and Laboratory Test - Hematologic+).
Anti-Diabetics/Insulin: Dose adjustments (decrease or increase) of insulin and anti-diabetic products may be required when administered concomitantly with pasireotide (see 7. Warning and Precautions - Endocrine and Metabolism, Glucose Metabolism).
Bromocriptine: Coadministration of SIGNIFOR LAR with bromocriptine may increase the blood levels of bromocriptine. Dose reduction of bromocriptine may be necessary.
Cyclosporine: Concomitant administration of cyclosporine with SIGNIFOR LAR may decrease the relative bioavailability of cyclosporine and, therefore, consider monitoring and dose adjustment of cyclosporine to maintain therapeutic levels (see 7 Warnings and Precautions - Monitoring and Laboratory Test - Cyclosporine).
Cytochrome P450/3A4 Interactions: Limited published data suggest that somatostatin analogs might have an indirect effect in decreasing the metabolic clearance of compounds metabolized by cytochrome P450 (CYP450) enzymes, via suppression of growth hormone secretion. The possibility that pasireotide may exert such an indirect effect cannot be excluded based on available data. Caution should be exercised when administering pasireotide concomitantly with drugs possessing a low therapeutic index and which are metabolized mainly by CYP3A4 (e.g. quinidine).
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Pasireotide is a second generation cyclohexapeptide, injectable somatostatin analogue. Like the natural peptide hormones somatostatin-14 and somatostatin-28 [also known as somatotropin release inhibiting factor (SRIF)], pasireotide exerts its pharmacological activity via binding to somatostatin receptors (SSTRs). There are five known human somatostatin receptor subtypes: SSTR 1, 2, 3, 4, and 5. These receptor subtypes are expressed in different tissues under normal physiological conditions. Somatostatin analogues bind to SSTR receptors with different potencies (Table 5). Pasireotide binds with high affinity to four of the five SSTRs: SSTR5˃SSTR2˃SSTR3˃SSTR1.
Table 5: Binding Affinities of Somatostatin (SRIF-14) and Pasireotide to the Five Human SSTR Receptor Subtypes (SSTR1-5)1
| Compound | SSTR1 | SSTR2 | SSTR3 | SSTR4 | SSTR5 | |||||
| Somatostatin (SRIF-14) | 0.93±0.12 | 0.15±0.02 | 0.56±0.1 7 | 1.5±0.4 | 0.29±0.0 4 | |||||
| Pasireotide | 9.3±0.1 | 1.0±0.1 | 1.5±0.3 | > 100 | 0.16±0.0 1 | |||||
| 1 Results are the mean+SEM of IC50 values expressed as nmol/L (nM). | ||||||||||
10.2. Pharmacodynamics
Somatostatin receptors are expressed in many tissues, especially in neuroendocrine tumors (e.g., growth hormone (GH) or adrenocorticotrophic hormone (ACTH) secreting pituitary adenomas), in which hormones are excessively secreted (e.g., GH in acromegaly and ACTH in Cushing’s disease).
Acromegaly
Pasireotide binds to SSTR2 and SSTR5 subtype receptors which may be relevant for inhibition of GH secretion.
Cushing’s disease
In vitro studies have shown that corticotroph tumor cells from Cushing’s disease patients display a high expression of SSTR5, whereas the other receptor subtypes are either not expressed or are expressed at lower levels. Pasireotide binds and activates the SSTRs of the corticotrophs in ACTH producing adenomas resulting in inhibition of ACTH secretion. The high affinity of pasireotide for four of the five SSTRs, especially to SSTR5, provides the basis for pasireotide to be an effective treatment for Cushing’s disease patients.
Cardiac Electrophysiology
The effects of pasireotide (administered subcutaneously; referred to as SIGNIFOR s.c.) on cardiac electrophysiology were assessed in two dedicated ECG assessment studies (see 7. Warnings and Precautions – Cardiovascular and Monitoring and Laboratory Tests, 8. Adverse Reactions, and 9.4 Drug-Drug Interactions).
ECG Study 1: In the first randomised, double-blind, placebo-controlled, crossover ECG assessment study, healthy volunteers (N=77) received treatment for 4 days with a supratherapeutic subcutaneous dose of pasireotide 1950 μg BID, followed by a 1950 μg morning dose on day 5. ECG assessments were performed at 10 time points on day 5. SIGNIFOR 1950 μg treatment was associated with statistically significant decreases in heart rate and prolongation of the Fridericia-corrected QT interval (QTcF=QT/RR0.33) at all timepoints on day 5. The maximum placebo-adjusted mean changes from baseline occurred at 2 h post-dosing and were -12.6 bpm (90% CI -13.9, -11.3) for heart rate and 17.5 ms (90% CI 15.5, 19.4) for the QTcF interval. SIGNIFOR 1950 μg treatment was also associated with statistically significant increases in the PR interval, with a maximum placebo-adjusted mean change from baseline of 6.9 ms (90% CI 5.4, 8.5) at 4 h post-dosing.
ECG Study 2: In a second randomised, double-blind, placebo-controlled, crossover ECG assessment study in healthy volunteers (N=105), subjects received treatment for 4 days with a therapeutic s.c. dose of SIGNIFOR 600 μg BID and a supratherapeutic subcutaneous dose of pasireotide 1950 μg BID, followed by 600 μg and 1950 μg morning doses on day 5. ECG assessments were performed at 11 time points on day 5.
In both the 600 μg and 1950 μg treatment arms, pasireotide was associated with statistically significant QTcF prolongation at all timepoints on day 5. The maximum placebo-adjusted mean change from baseline occurred at 2 h post-dosing in both treatment arms and was 11.8 ms (90% CI 10.0, 13.5) in the 600 μg treatment arm and 14.0 ms (90% CI 12.3, 15.8) in the 1950 μg arm.
The mechanism for the observed QT prolongation is not known.
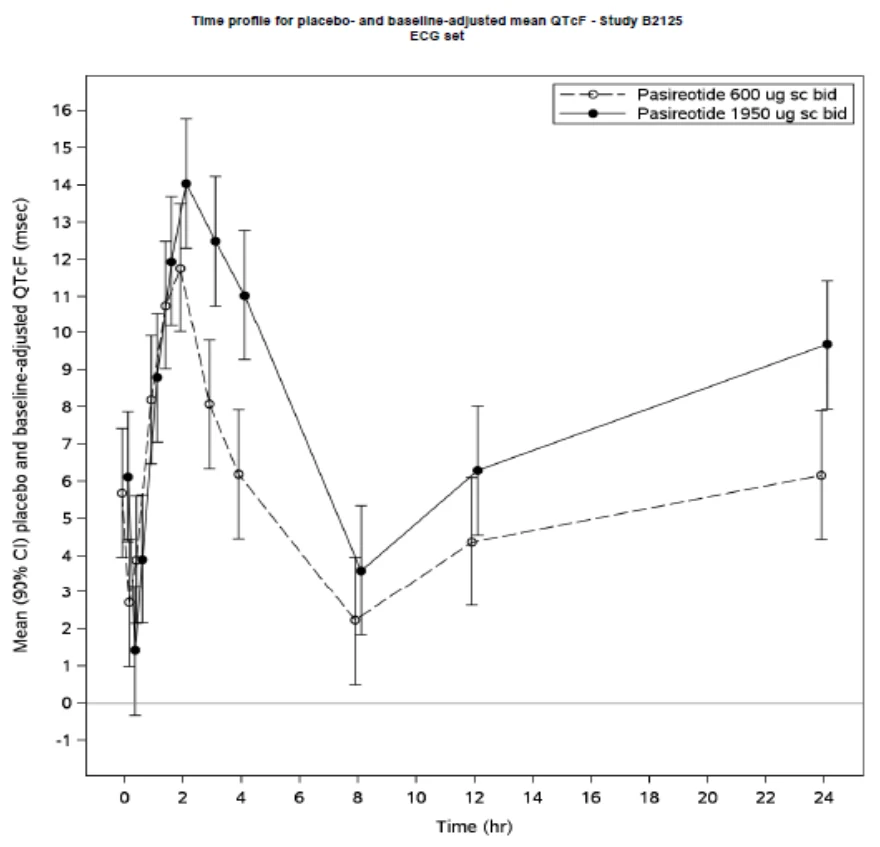
In both the 600 μg and 1950 μg treatment arms, SIGNIFOR s.c. was associated with statistically significant reductions in heart rate at all timepoints on day 5. The maximum placebo-adjusted mean change from baseline was -10.4 bpm (90% CI -11.5, -9.2) at 1 h post-dosing in the 600 μg treatment arm and -14.9 bpm (90% CI -16.1, -13.8) in the 1950 μg arm.
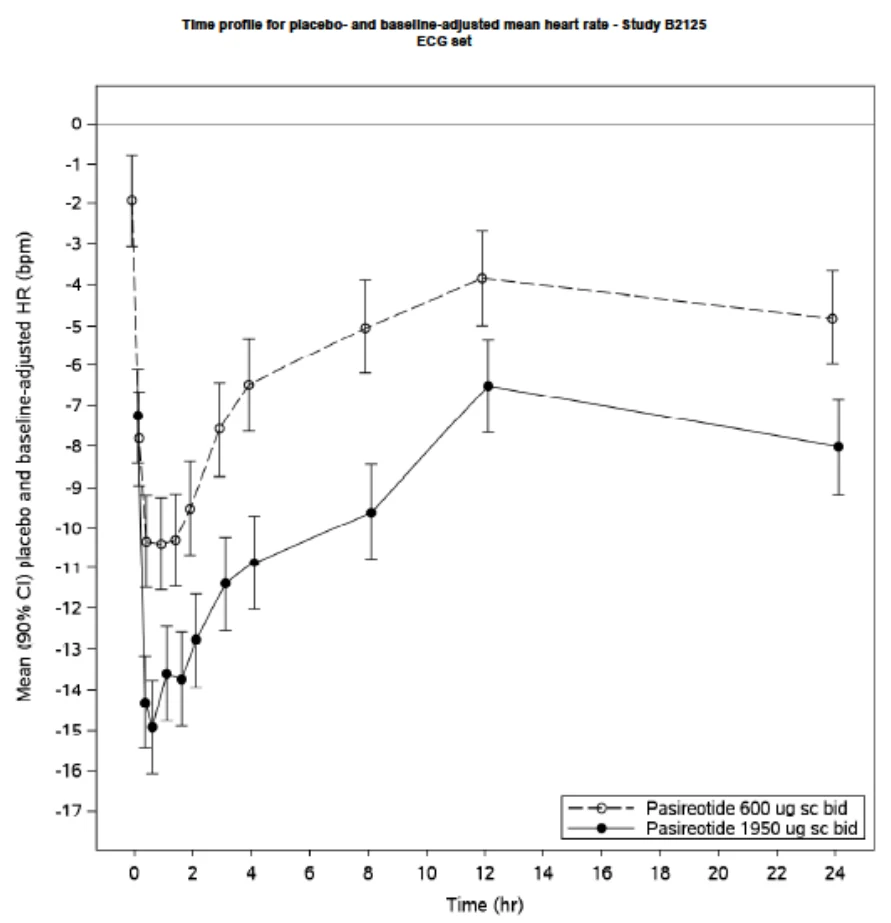
Statistically significant prolongation of the PR interval occurred from 0.25 to 8 h post-dosing in the SIGNIFOR s.c. 600 μg arm and at all timepoints in the SIGNIFOR s.c. 1950 μg arm on day 5. The maximum placebo-adjusted mean change from baseline occurred at 2 h post-dosing in both treatment arms and was 6.1 ms (90% CI 4.6, 7.6) in the 600 μg arm and 9.9 ms (90% CI 8.4, 11.4) in the 1950 μg arm.
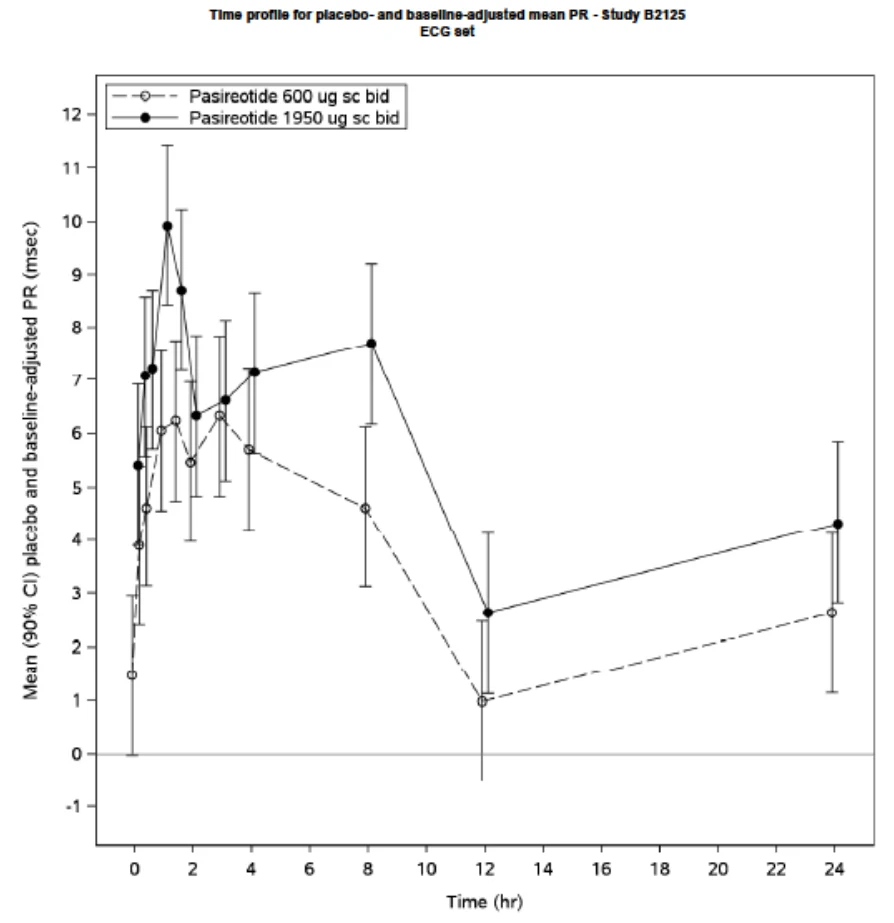
On the basis of population pharmacokinetic modelling, the predicted steady-state mean peak plasma concentration for the maximum SIGNIFOR LAR dose of 60 mg dose every 28 days in acromegaly patients would be 25.8 ng/mL, which is similar to the observed steady-state mean peak concentration (24.3 mg/mL) of SIGNIFOR s.c. 600 μg twice a day and below the observed steady-state mean peak concentration (80.6 ng/mL) of the 1,950 μg twice a day dose in ECG Study 2. The predicted peak concentrations for the maximum SIGNIFOR LAR dose of 40 mg in Cushing’s disease patients is 14 ng/mL, which is below the observed peak concentrations of Signifor s.c. described above.
Clinical studies in patients with acromegaly have shown that GH and IGF-1 levels markedly decrease by Month 3 with monthly intramuscular (i.m.) injections of SIGNIFOR LAR varying from 20 mg to 60 mg and the reduction is sustained overtime.
PK/PD analyses for efficacy based on Emax model and logistic regression model have shown that higher exposure of pasireotide is associated with greater suppression of GH and IGF-1 levels, and that pasireotide is superior to octreotide in terms of suppression of IGF-1. The results of the PK/PD analyses are consistent with the GH and IGF-1 response rates observed in studies C2305 and C2402.
PK/PD analyses for safety have shown that the odds of post-baseline hyperglycemia increases moderately with increasing pasireotide exposure from 40 mg to 60 mg. In addition, higher baseline HbA1c and higher baseline FPG are associated with a higher probability of developing hyperglycemia. No correlation was found between pasireotide exposures and QT or liver functions.
10.3. Pharmacokinetics
After a single intramuscular (i.m.) injection of SIGNIFOR LAR varying from 10 mg to 60 mg in healthy volunteers, PK profiles showed an initial burst release (Cmax,p1) at 12 hours post injection on Day 1 (Tmax,p1), followed by a dip from Day 2 to Day 7, then a slow increase to maximum concentration (Cmax,p2) at Day 20 (Tmax,p2), followed by a declining phase over the next seven weeks. The Cmax,p2 and AUCinf for 60 mg SIGNIFOR LAR dose, range between 15.8-29 ng/mL and 7971-13395 ng.hr/mL, respectively. The PK profiles of SIGNIFOR LAR were similar between Western and Asian subjects. PK exposures (Cmax,p2 and AUCinf) were approximately dose proportional from 10 mg to 60 mg. The apparent clearance (CL/F) of pasireotide LAR was 4.5 to 8.5 L/hr. The apparent volume of distribution (Vz/F) was large (>100 L). The apparent terminal half-life (T1/2) for SIGNIFOR LAR was approximately 16 days. The relative bioavailability of SIGNIFOR LAR to SIGNIFOR was 106 – 148%. Pharmacokinetics (PK) is comparable between healthy volunteers and acromegaly patients. PK exposures reached steady state after 3 injections
Table 6: Summary of SIGNIFOR LAR (monthly dosing) Pharmacokinetic Parameters in Acromegaly Patients
| Dose (mg) | Ctrough,ss (ng/mL)1 | Cmaxp2,ss (ng/mL)1 | Tmax,p2 (days)2 | AUC0-28d,ss (hr*ng/mL)1 |
| 20 | 3.77 (1.94) | 5.04 (2.00) | 21 | 2749 (1099) |
| 40 | 7.16 (3.13) | 8.03 (3.17) | 21 | 4788 (1974) |
| 60 | 13.3 (8.9) | 17.8 (8.9) | 22 | 8700 (3822) |
1 Data expressed as mean (SD) values and from the third dose at steady state 2 Data expressed as median values from the first dose. | ||||
Pasireotide for intramuscular use is formulated as microspheres for long-acting release. After a single injection, the plasma pasireotide concentration shows an initial burst release on the injection day, followed by a dip from Day 2 to Day 7, then a slow increase to the maximum concentration around Day 21, and a slow declining phase over the next weeks, concomitant with the terminal degradation phase of the polymer matrix of the dosage form.
Absorption:
No studies have been conducted to evaluate the absolute bioavailability of pasireotide in humans. Food effect is unlikely to occur since SIGNIFOR LAR is administered via the parenteral route. The relative bioavailability of SIGNIFOR LAR compared to SIGNIFOR s.c. is 106-148%.
Distribution:
In healthy volunteers, pasireotide administered as SIGNIFOR LAR is widely distributed with a large apparent volume of distribution (Vz/F >100 L). Distribution between blood and plasma is concentration independent and shows that pasireotide is primarily located in the plasma (91%). Plasma protein binding is moderate (88%) and independent of concentration.
Metabolism:
Pasireotide was shown to be highly metabolically stable. In healthy volunteers, pasireotide in its unchanged form is the predominant form found in plasma, urine, and feces.
Excretion:
Pasireotide is eliminated mainly via hepatic clearance (biliary excretion) with a small contribution of the renal route. In a human ADME study with pasireotide administered as SIGNIFOR s.c. with a single dose of 600 microgram, 55.9 ± 6.63% of the radioactivity dose was recovered over the first 10 days post dosing, including 48.3 ± 8.16% of the radioactivity in feces and 7.63 ± 2.03% in urine.
The apparent clearance (CL/F) of pasireotide administered as SIGNIFOR LAR in healthy volunteers is on average 4.5 to 8.5 L/h. Based on population pharmacokinetic (PK) analyses, the estimated CL/F was approximately 4.8 to 6.5 L/h for typical Cushing’s disease patients, and approximately 5.6 to 8.2 L/h for typical acromegaly patients.
Steady-state pharmacokinetics, Dose proportionality, and Accumulation:
Following monthly (every 28 days) i.m. injections of 20 mg, 40 mg, and 60 mg SIGNIFOR LAR, a steady state was achieved after three monthly doses in acromegaly patients. PK exposures of SIGNIFOR LAR were approximately dose proportional (steady-state trough concentration; Ctrough, ss) from 10 mg to 60 mg in patients. Peak-to-trough ratio (<1.5) and accumulation (ratio of 1.5-2.0) of SIGNIFOR LAR were low to moderate on multiple dosing.
Special Populations and Conditions
Pediatrics (<18 years of age): No studies have been performed in pediatric patients (see 1.1 Pediatrics, 7.1.3 Pediatrics, and 4.1 Dosing Considerations - Special Populations, Pediatrics).
Geriatrics (≥65 years of age): Age is not a significant covariate in the population PK analysis of patients. Therefore, age is not expected to significantly impact circulating levels of pasireotide. Efficacy and safety data on patients older than 65 years are limited (see 1.2 Geriatrics , 7.1.4. Geriatrics, and 4.1 Dosing Considerations - Special Populations, Geriatrics).
Gender: Female acromegaly patients had a higher exposure of 32% and 51% compared to male patients in studies with medical treatment naïve patients and inadequately controlled patients, respectively; these differences in exposure were not clinically relevant based on efficacy and safety data. Population PK analyses of pasireotide administered as SIGNIFOR LAR in Cushing’s disease patients demonstrates that gender is not a significant covariate and suggests that gender does not influence PK parameters. No dose adjustment is required based on gender.
Race: Population PK analyses of pasireotide administered as SIGNIFOR LAR suggest that race does not have clinically relevant influence on PK parameters. No dose adjustment is required based on race.
Hepatic Insufficiency: SIGNIFOR LAR is contraindicated in patients with moderate or severe hepatic insufficiency (see 2. Contraindications). In a clinical study with single dose of pasireotide administered as SIGNIFOR s.c. in subjects with impaired hepatic function (Child-Pugh A, B and C), subjects with moderate and severe hepatic impairment (Child-Pugh B and C) showed significantly higher exposures than subjects with normal hepatic function. Upon correction for covariate effect (age, BMI, and albumin) AUCinf was increased by 60% and 79%, Cmax increased by 67% and 69%, and CL/F decreased by 37% and 44%, respectively, in the moderate and severe hepatic impairment groups relative to the control group.
Renal Impairment: No dose adjustment is required in patients with mild or moderate impaired renal function. SIGNIFOR LAR should be used with caution in patients with severe renal impairment.
In a clinical study with single dose administration of 900 µg pasireotide as SIGNIFOR s.c. in subjects with impaired renal function, the degree of renal impairment did not have a significant impact on the pharmacokinetics of pasireotide. The AUC0-inf decreased by 22%, 14%, and 1% for mild, moderate, and severe renally impaired subjects and increased by 25% in ESRD subjects compared to normal subjects adjusted for age, gender, and weight as covariates. The Cmax decreased by 28%, 23%, 19%, and 10% for mild, moderate, severe renally impaired, and ESRD subjects compared to normal subjects adjusted for age, gender, and weight as covariates. However, increases in unbound pasireotide AUCinf,u of 1.85, 2.41, 2.96 fold and Cmax,u of 1.36, 2.00, 3.01 fold were observed in patients with moderate, severe renal impairment, and ESRD. Grade 3 and Grade 4 increases in amylase, lipase, and uric acid, and grade 3 decreases in hemoglobin were also observed in subjects with severe renal impairment and ESRD. Hence, caution is recommended for the use of pasireotide in patients with severe renal impairment and ESRD (see 7. Warnings and Precautions – Renal, Monitoring and laboratory tests, and 4.1 Dosing Considerations - Special Populations, Renal Impairment).
Body weight: PK exposures had a slight correlation with body weight in the study with medical treatment naïve patients (approximately 39% increase for 40 kg decrease in body weight), but not in the study with inadequately controlled patients. These changes are not clinically significant. No dose adjustment is required based on body weight.
Genetic polymorphism: The effect of genetic polymorphism on the pharmacokinetics of SIGNIFOR LAR has not been established.
11. Storage, Stability and Disposal
Store at 2 to 8°C. Do not freeze.
Prior to reconstitution, the injection kit should be removed from the fridge and equilibrated to room temperature for a minimum of 30 minutes and maximum of 24 hours.
The suspension should be administered immediately after reconstitution.
SIGNIFOR LAR (pasireotide as pamoate) must be kept out of the reach and sight of children.
12. Special Handling Instructions
SIGNIFOR LAR powder for suspension for injection is supplied in a 6 mL brownish glass vial, consisting of drug loaded poly (D,L-lactide-co-glycolide) microparticles to be suspended in an aqueous vehicle prior to injection.
SIGNIFOR LAR (pasireotide as pamoate) should be administered by a trained health care professional. For instructions on the use of SIGNIFOR LAR (pasireotide as pamoate) vials, refer to 4.3 Reconstitution.
Special precautions for disposal
Any unused product or waste material should be disposed of in accordance with local requirements.
Incompatibilities
SIGNIFOR LAR powder for suspension for injection is to be used as a single dose unit, without any dilution with other products. Therefore, no compatibility data with other products have been generated.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: Pasireotide pamoate
Chemical name: (2-Aminoethyl)carbamic acid (2R,5S,8S,11S,14R,17S,19aS)-11- (4 aminobutyl)-5-benzyl-8-(4-benzyloxybenzyl)-14-(1H-indol-3- ylmethyl)-4,7,10,13,16,19-hexaoxo-17-phenyloctadecahydro- 3a,6,9,12,15,18-hexaazacyclopentacyclooctadecen-2-yl ester pamoic acid salt
Molecular formula and molecular mass: C58H66N10O9 • C23H16O6
1047.21 + 388.37 = 1435.58
Structural formula:
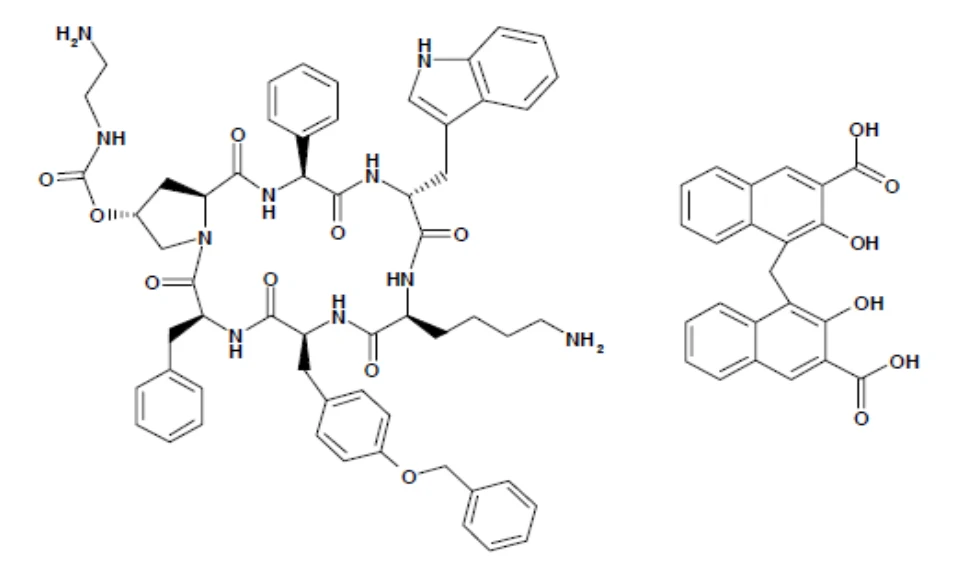
Physicochemical properties: Pasireotide pamoate, a novel cyclohexapeptide, is a somatostatin analogue. It is a white to slightly yellowish powder (lyophilisate). The aqueous ionization constants (pKa) of pasireotide base were determined by potentiometric titration in water/dioxane in 0.15 M KCl at 25°C. The values are: pKa1 = 10.2, pKa2 = 9.1. Further evaluation of the pKa with Pasireotide pamoate has not been possible due to its low solubility in water.
14. Clinical Trials
14.1. Clinical Trials by Indication
Acromegaly
Study Demographics and Trial Design
Table 7: Summary of Patient Demographics for Clinical Trials in Patients With Acromegaly
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| C2305 | Randomized, double-blind, controlled, multicenter | Pasireotide LAR 40 mg or octreotide LAR 20 mg every 28 days for a total of 12 i.m. injections in the 12 months core phase. SIGNIFOR® LAR® 40 mg: n = 176 SANDOSTATIN® LAR® 20 mg: n = 182 | N=358 | 45.4 (18-85) | M= 48% F= 52% |
| C2402 | Randomized, three arm study of double-blind SIGNIFOR LAR vs open-label SANDOSTATIN® LAR® or lanreotide ATG, controlled, multicenter | Pasireotide LAR 40 or 60 mg i.m. injections, or SANDOSTATIN® LAR® 30 mg i.m. injection or Somatuline (lanreotide) ATG 120 mg deep s.c. injection, every 28 days for 24 weeks SIGNIFOR LAR 40 mg: n = 65 SIGNIFOR LAR 60 mg: n = 65 SANDOSTATIN® LAR® 30 mg or SOMATULINE® AUTOGEL® 120 mg: n = 68 | N=198 | 45 (18-83) | M = 44% F = 56% |
Medically Naïve Patients, Study C2305
A Phase III multicenter, randomized, blinded study was conducted to assess the safety and efficacy of SIGNIFOR LAR vs. SANDOSTATIN® LAR® in medically naïve patients with active acromegaly. A total of 358 patients were randomized and treated. Patients were randomized in a 1:1 ratio to one of two treatment groups in each of the following two strata: 1) patients who have undergone one or more pituitary surgeries but have not been treated medically or 2) de-novo patients presenting a visible pituitary adenoma on MRI who refuse pituitary surgery or for whom pituitary surgery is contraindicated.
The two treatment groups were well balanced in terms of baseline demographics and disease characteristics. In the overall study population, 58% of patients were patients without previous pituitary surgery (de-novo). Females constituted 52% of the patients in both treatment groups, the average age of patients was 45 years and 60% of patients were Caucasian. Baseline median (range) GH was 8.8 (0.8 – 200) microgram/L and 10.1 (0.6 – 169.9) microgram/L for SIGNIFOR LAR and active comparator, respectively. Baseline median standardized (range) IGF-1 (defined as IGF-1 value divided by the ULN) values were 2.9 (0.9 – 6.9) and 2.9 (0.8 – 7.3), for SIGNIFOR LAR and active comparator, respectively.
The starting dose was 40 mg for SIGNIFOR LAR and 20 mg for SANDOSTATIN® LAR®. Dose increase for efficacy was allowed at the discretion of the investigators after three and six months of treatment if biochemical parameters showed a mean GH ≥2.5 microgram/L and/or IGF-1 >ULN (age and sex related). Maximum allowed dose was 60 mg for SIGNIFOR LAR and 30 mg for SANDOSTATIN® LAR®.
The primary efficacy endpoint was the proportion of patients with a reduction of mean GH level to <2.5 microgram/L and the normalization of IGF-1 to within normal limits (age and sex related) at Month 12. The study met its primary efficacy endpoint. As shown in Table 8, statistically significant (p=0.007) higher proportion of patients achieving a reduction of mean GH level to <2.5 microgram/L and the normalization of IGF-1 to within normal limits was observed with SIGNIFOR LAR compared to SANDOSTATIN® LAR®.
Table 8: Results at Month 12 (Study C2305)
| SIGNIFOR LAR n (%) N=176 | SANDOSTATIN® LAR® n (%) N=182 | p-value | ||||
| GH<2.5 microgram/L and normalized IGF-11 | 31.3% | 19.2% | p=0.007 | |||
| GH<2.5 microgram/L and IGF-1 ≤ULN2 | 35.8% | 20.9% | - | |||
| Normalized IGF-1 | 38.6% | 23.6% | p=0.002 | |||
| GH<2.5 microgram/L | 48.3% | 51.6% | p=0.536 | |||
1 Primary endpoint (patients with IGF-1< lower limit of normal (LLN) were not considered as “responders”) 2 ULN = upper limit of normal | ||||||
Biochemical control was achieved by Month 3 by a higher proportion of patients in the SIGNIFOR LAR arm than in the SANDOSTATIN® LAR® arm (30.1% and 21.4%, respectively), and was maintained in all subsequent evaluations during the core phase.
During the extension phase, 74 patients continued receiving SIGNIFOR LAR and 46 patients continued with SANDOSTATIN® LAR® treatment. At Month 25, 48.6% of patients in the SIGNIFOR LAR group and 45.7% in the SANDOSTATIN® LAR® group achieved biochemical control.
Inadequately Controlled Patients, Study C2402
Study C2402 was a Phase III, multicenter, randomized, parallel-group, three-arm study of double-blind SIGNIFOR LAR 40 mg and SIGNIFOR LAR 60 mg versus open-label SANDOSTATIN® LAR® 30 mg or lanreotide ATG 120 mg in patients with inadequately controlled acromegaly. A total of 198 patients were randomized to receive SIGNIFOR LAR 40 mg (n=65), SIGNIFOR LAR 60 mg (n=65), or active control (n=68). 192 patients were treated. A total of 181 patients completed the core phase (24 weeks) of the study.
Inadequately controlled patients were defined as patients with a mean GH concentration of a 5-point profile over a 2-hour period >2.5 microgram/L and sex- and age-adjusted IGF-1 >1.3 × upper limit of normal (ULN). Patients had to be treated with maximum indicated doses of SANDOSTATIN® LAR® (30 mg) i.m. injection or lanreotide ATG (120 mg) deep s.c. injection for at least 6 months prior to randomization.
Baseline demographic and disease characteristics were balanced between the treatment arms, with a mean age around 45 years, approximately equal proportion of men and women (in the overall study population, 56% were females and 81% were Caucasians), and median time since diagnosis of approximately 4 years. Three-quarters of patients had previously been treated with SANDOSTATIN® LAR® and a quarter with lanreotide ATG. Nearly half of the patients had additional prior medical treatment for acromegaly other than somatostatin analogues. Two-thirds of all patients had undergone prior surgery (77%, 63%, and 60% in the SIGNIFOR LAR 40 mg, 60 mg, and active control arms, respectively). Three percent (3%) of patients in the SIGNIFOR LAR arms and 7% of patients in the active control arm had prior radiation therapy. Baseline median (range) GH was 7.1 (1.0-200) mcg/L, 5.3 (1.4-113.8) mcg/L, and 6.1 (1.0-92.4) mcg/L in the 40 mg, 60 mg, and active control groups, respectively. Baseline median standardized IGF-1 (defined as IGF-1 value divided by the ULN) values were 2.3, 2.6, and 2.9, respectively.
The primary efficacy endpoint was to compare the proportion of patients achieving biochemical control (defined as mean GH levels <2.5 microgram/L and normalization of sex- and age-adjusted IGF-1) at week 24 with SIGNIFOR LAR 40 mg or 60 mg versus continued treatment with active control (SANDOSTATIN® LAR® 30 mg or lanreotide ATG 120 mg), separately. The study met its primary efficacy endpoint for both SIGNIFOR LAR doses. The proportion of patients achieving biochemical control, was 15.4% (p=0.0006) and 20.0% (p<0.0001) for SIGNIFOR LAR 40 mg and 60 mg, respectively at 24 weeks compared with zero in the active control arm (Table 9).
Table 9: Results at Month 6 (Study C2402)
SIGNIFOR LAR 40 mg N=65 n (%), p value | SIGNIFOR LAR 60 mg N=65 n (%), p value | Active Control N=68 n (%) | ||||
| GH<2.5 microgram/L and normalized IGF-11 | 10 (15.4%), p=0.0006 | 13 (20.0%), p<0.0001 | 0 (0%) | |||
| Normalization of IGF-1 | 16 (24.6%), p<0.0001 | 17 (26.2%), p<0.0001 | 0 (0%) | |||
| GH<2.5 microgram/L | 23 (35.4%) | 28 (43.1%) | 9 (13.2%) | |||
| 1 Primary endpoint (patients with IGF-1< lower limit of normal (LLN) were not considered as “responders”) | ||||||
Biochemical control was achieved by Month 3 in 15.4% and 18.5% of patients in the SIGNIFOR LAR 40 mg and 60 mg arms, respectively, and was maintained up to Week 24, which is consistent with what was observed in medically naïve patients in Study C2305.
Cushing's Disease
Study Demographics and Trial Design
Study G2304
A phase III, randomized, double-blind, multicenter study was conducted to evaluate the safety and efficacy of two dose regimens of SIGNIFOR LAR over a twelve month treatment period in Cushing’s disease patients with persistent or recurrent disease, or de novo patients who were not considered candidates for pituitary surgery (patients for whom surgery was not indicated or who refused surgery).
The study enrolled 150 patients with a screening mean urinary free cortisol (mUFC) level of between 1.5 and 5 times upper limit of normal (≥1.5 and ≤5 x ULN), who were randomized in a 1:1 ratio to receive a starting dose of either 10 mg (N=74) or 30 mg (N=76) intramuscular SIGNIFOR LAR once every 28 days. Randomization was stratified by values of screening mUFC (1.5 to <2xULN versus 2 to 5xULN, respectively).
After four months of treatment, patients who had a mUFC ≤1.5 x ULN continued on the blinded starting dose to which they were randomized and patients with a mUFC >1.5 x ULN had their doses increased in a blinded manner from 10 mg to 30 mg, or from 30 mg to 40 mg, provided there were no tolerability concerns. Additional dose increases (up to a maximum of 40 mg) were allowed at Months 7 and 9 (by one dose level if the mUFC was >1xULN). Dose reduction by one dose level for tolerability was allowed in a blinded fashion during the first seven months, with a minimum dose level of 5 mg. After the first seven months, blinded down titration of more than one dose level was allowed at any month.
Baseline demographics and disease characteristics were generally well balanced between the two randomized dose groups and consistent with the epidemiology of the disease. The mean age of patients was approximately 38.5 years with a predominance of female patients (78.7%). Few patients (3 patients, 2.0%) were ≥ 65 years of age and 55.3% of patients were Caucasian. The majority of patients (82.0%) had undergone previous pituitary surgery. The mean and median baseline 24-hour mUFC were 470 nmol/24 hours and 396.9 nmol/24 hours, respectively, (ULN: 166.48 nmol/24 hours). 116 (77%) of all randomized patients completed seven months of treatment and 104 (69.3%) patients completed twelve months of treatment and had the option to enter an extension phase to continue to receive SIGNIFOR LAR if they benefited from treatment.
At baseline, 60 (40%), 24 (16%), and 66 (44%) of all randomized patients were diabetic, pre-diabetic, or normoglycemic, respectively. At their last observed study assessment, 88% of patients who were normoglycemic (HbA1c ˂5.7%) at baseline became either pre-diabetic (HbA1c 5.7% to ˂6.5%) or diabetic (HbA1c ˃6.5%). HbA1c levels stabilized with the addition of antihyperglycemic treatment, but did not return to baseline values.
The primary efficacy endpoint was the proportion of patients in each dose arm who were mUFC responders (24-hour mUFC ≤ULN) after seven months of treatment, regardless of dose up-titration status at Month 4. The key secondary endpoint was the proportion of patients in each dose arm who were mUFC responders after seven months of treatment and who did not up-titrate the dose prior to Month 7. The pre-specified boundary of the lower limit of the 95% confidence interval for efficacy for both the primary and key secondary endpoints was 15%. Patients with missing mUFC assessment at Month 7 were considered as non-responders. Other secondary endpoints included changes from baseline in 24-hour UFC, plasma ACTH, serum cortisol levels, clinical signs and symptoms of Cushing’s disease, and health-related quality of life (HRQL) as measured by the SF-12v2 and CushingQoL tools. All analyses were conducted based on the randomized dose groups.
Results
The study met the primary efficacy objective for both dose groups. Patients were considered responders if they remained on treatment until at least Month 7 and achieved a Month 7 mUFC ≤ 1x ULN, regardless of up-titration at Month 4. At Month 7, mUFC response was achieved in 39.2% (95% CI 28.0 to 51.2) and 40.8% (95% CI 29.7 to 52.7) of patients randomized to pasireotide LAR at starting doses of 10 mg and 30 mg once every 28 days, respectively. The response rates were higher in the lower mUFC stratum (mUFC ≥1.5 x ULN to ≤2 x ULN) than in the higher mUFC stratum (mUFC >2 x ULN to ≤5 x ULN), respectively (Table 10). The responder rate at Month 12 was 35.1% (26/74) and 25.0% (19/76) in the 10 mg and 30 mg starting dose groups, respectively.
Table 10: Response Rates at Month 7 per Randomized Dose Group and According to Screening mUFC – Primary Efficacy Analysis
| Pasireotide LAR | Pasireotide LAR | |||||
| 10 mg q28d | 30 mg q28d | |||||
| Screening mUFC category | n/N (%) | n/N (%) | ||||
| 95% CI | 95% CI | |||||
| All patients1 (Primary efficacy analysis) | 29/74(39.2) | 31/76 (40.8) | ||||
| (28.0, 51.2) | (29.7, 52.7) | |||||
| ≥1.5 x ULN to ≤2 x ULN | 11/25 (44.0) | 13/25 (52.0) | ||||
| (24.4, 65.1) | (31.3, 72.2) | |||||
| >2 x ULN to ≤5 x ULN | 18/49 (36.7) | 18/51 (35.3) | ||||
| (23.4, 51.7) | (22.4, 49.9) | |||||
| 1 There were 17 (23.0%) patients in the 10 mg dose group and 9 (11.8%) patients in the 30 mg dose arm with missing value mUFC assessments at Month 7 who were classified as non-responders. | ||||||
The study met the key secondary efficacy objective for both dose groups. At Month 4, 31/74 (41.9%) and 28/76 (36.8%) patients were up-titrated in the pasireotide LAR 10 mg and 30 mg arms, respectively. When all patients who up-titrated prior to Month 7 were counted as non-responders, Month 7 mUFC response was observed in 25.7% (95% CI 16.2 to 37.2) and 31.6% (95% CI 21.4 to 43.3) of patients randomized to pasireotide LAR at starting doses of 10 mg and 30 mg once every 28 days, respectively.
A supportive analysis for the primary end point was conducted at Month 7 for the combined proportion of controlled patients (who attained mUFC ≤1.0 x ULN) or partially controlled patients (who had at least 50% reduction in mUFC from baseline). The combined rate of controlled and partially controlled responders at Month 7 constituted 44.6% and 53.9% of patients randomized to the 10 mg and 30 mg dose groups, respectively (Table 11).
Table 11: Response Rates at Month 7 per Randomized Dose Group - Supportive Efficacy Analysis
| Response category | Pasireotide LAR 10 mg q28d N=74 n (%) | Pasireotide LAR 30 mg q28d N=76 n (%) |
| Controlled (mUFC ≤ ULN) | 29 (39.2%) | 31 (40.8%) |
| Partially controlled (≥ 50% reduction in mUFC) | 4 (5.4%) | 10 (13.2%) |
| Combined | 33 (44.6%) | 41(53.9%) |
In both dose groups, SIGNIFOR LAR resulted in a decrease in mUFC after one month of treatment, and this was maintained over time (Figure 1).
Figure 1: Mean (±SE) Urinary Free Cortisol (nmol/24h) at Time Points up to Month 12 by Randomized Dose Group
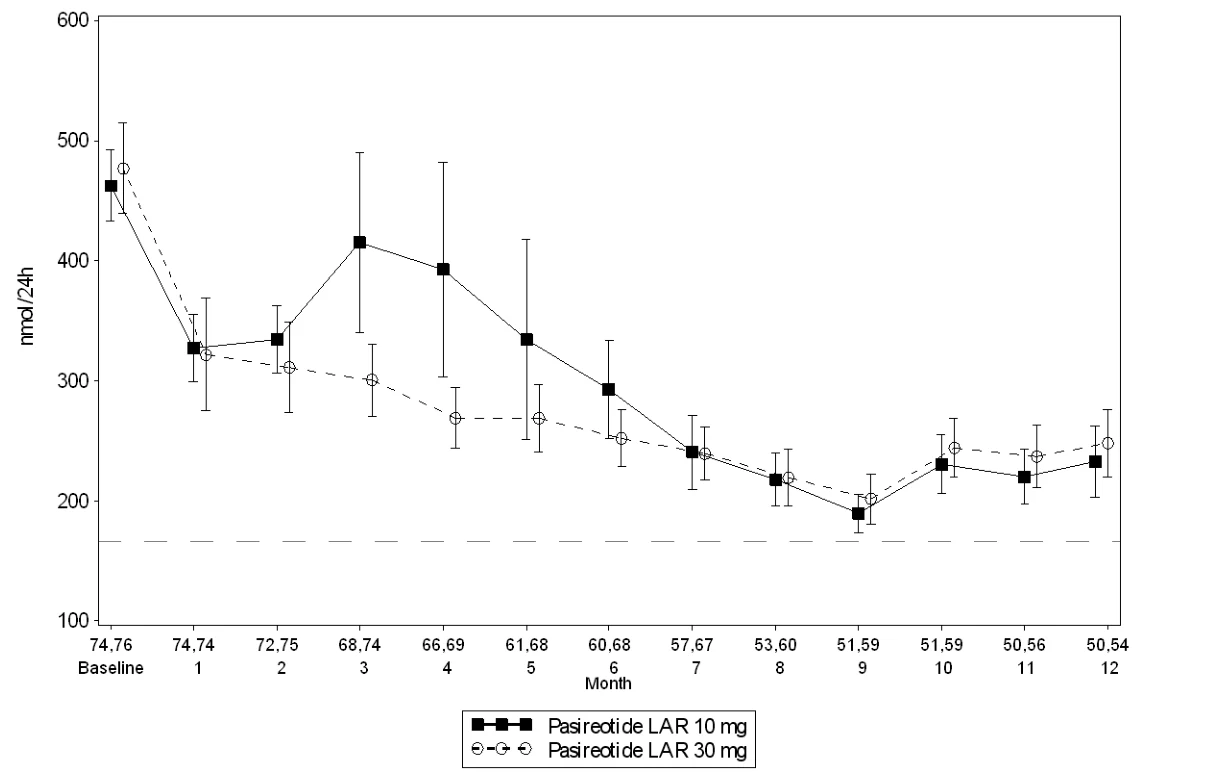
-The numbers of patients contributing to the mean and standard error (SE) for each month are displayed under the X-axis (10 mg/30 mg). This analysis includes scheduled visits only.
-The dotted line (----) is the ULN for the UFC assay (166.48 nmol/24h)
Decreases in median mUFC levels at Month 7 compared to baseline, as measured by overall percentage of reduction, are shown in Table 12. Reductions in serum cortisol and plasma ACTH levels were also observed at Months 7 and 12 for each dose group.
Table 12: Median Percentage Change from Baseline in Mean Urinary Free Cortisol (mUFC) at Month 7 by Randomized Dose Group
| Pasireotide LAR 10 mg q28d % change | Pasireotide LAR 30 mg q28d % change | |||||||
| mUFC levels (nmol/24hr) Baseline | N | 74 | 76 | |||||
| Mean (SD) | 462.6 (256.41) | 477.1 (331.75) | ||||||
| Median (min, max) | 409.8 (44.7, 1432.9) | 371.6 (50.8, 1670) | ||||||
| Median (min, max) change in mUFC (% from baseline)1 | Month 7 | -41.3% (-47.9, -11.4) | -41.4% (-53.0, -22.4) | |||||
| 1 Median % change from baseline in mUFC are calculated by imputing missing values with the worst observed % change in mUFC at Month 7 within each treatment group. | ||||||||
Decreases in supine systolic and diastolic blood pressure and in body weight were observed in both dose groups at Month 7. Overall reductions in these parameters tended to be greater in patients who were mUFC responders. Similar trends were observed at Month 12.
At Month 7, the majority of patients demonstrated either improvement in or stable signs of Cushing’s disease compared to baseline. Facial rubor improved in 43.5% (47/108) of patients, and more than a third of patients demonstrated improvement in supraclavicular fat pad (34.3%) and dorsal fat pad (34.6%). Similar results were recorded at Month 12.
Quality of life was assessed using the generic quality of life measure (SF-12v2 General Health Survey) and the disease specific patient reported outcome measure (CushingQoL). Improvements were observed in both dose groups for CushingQoL and the Mental Component Summary (MCS) of SF-12v2, but not for the Physical Component Summary (PCS) of SF-12-v2.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology
Single dose toxicity
The acute toxicity of pasireotide was assessed in rats and mice at 15 and 30 mg/kg by the s.c. route. Lethalities were not observed.
Repeat dose toxicity
Rats
The pivotal rodent repeat-dose toxicity study was conducted in male and female rats. Animals were administered pasireotide by s.c. injection once daily at 0.0008, 0.024, 0.08 and 0.24 mg/kg/day for 26 weeks. When compared with human AUC values at 900 µg bid, these dose levels provide an exposure margin of 0.07, 0.24 (0.33 and 0.15 for males and females, respectively), 0.49, 1.92, respectively. The NOAEL was considered to be 0.024 mg/kg/day based on histological alterations in the pituitary (males) and the genital tract (females). Additionally, in the 26 week (6 cycle) rat study, i.m. administration of 3.125 and 6.25 mg pasireotide LAR led to AUC0-28d of 620.8 and 1062.5 ng.d/mL after the first cycle, leading to exposure multiples of 1.3 and 2.3-fold for AUC0-28d over the systemic exposure at human dose of 60 mg.
All pasireotide-mediated effects were considered a result of the drug’s pharmacology and all changes demonstrated reversibility following a drug-free period. Decreased body weight was observed in males (from 0.008 mg/kg) and females (0.24 mg/kg). In males, decreased pituitary weight and decreased cytoplasmic mass of acidophile cells/somatotrophs was observed at doses >0.024 mg/kg. In females, alterations in the genital tract (decreased number of corpora lutea, vaginal mucosal hyperplasia or hypertrophy of mucification, vaginal hypertrophy) consistent with prolongation of the estrous cycle were observed at doses ≥0.08 mg/kg.
Inhibitory effects on lymphoid and hematopoietic organs were observed and included decrease thymus weight and cellularity as well as decreased hematopoietic activity of the spleen and bone marrow. A lack of new bone formation beneath the epiphyseal plate of the tibia and femur was observed. Serum biochemistry changes (increased ALT, decreased albumin) and decreased liver weight suggested possible effects on the liver at high dose levels, possibly as a secondary result to the decrease in IGF-1. Changes in coagulation parameters (increased PT and APTT) noted in females are likely related to the pharmacologic effect of pasireotide, probably through modification of the liver production of coagulating factors regulated by GH.
The results of the pasireotide LAR studies demonstrated systemic effects that are similar to that by the s.c. formulation. The microscopic changes in target organs (pituitary, adrenal and thyroid glands, pancreas, bones and bone marrow) are consistent with the pharmacologic activity of somatostatin analogues.
Monkeys
The pivotal non-rodent repeat-dose toxicity study was conducted in male and female monkeys. Animals were administered pasireotide at 0.4, 1.6, and 3.2 mg/kg/day for 39 weeks. When compared with human AUC values at 900 µg bid, these dose levels provide an exposure margin of 12.2, 39.0 and 96.1 for males, and 13.3, 54.7 and 102.6 for females. The NOAEL was considered to be 1.6 mg/kg/day based on histological alterations in the pituitary (increased acidophilia in the pars distallis), thyroid (small follicles), large intestine (distension with firm fecal material), and injection site reactions. All pasireotide-mediated effects were considered a result of the drug’s pharmacology and all changes demonstrated reversibility following a drug-free period.
Carcinogenicity
The carcinogenic potential of pasireotide was assessed by the s.c. route in the 26-week transgenic RasH2 mouse model (dose levels: 0, 0.5, 1.0, 2.5 mg/kg/day) and the 2-year rat bioassay (dose levels: 0, 0.01, 0.05, 0.3 mg/kg/day). Pasireotide was not carcinogenic in either model.
Genotoxicity
Pasireotide did not exhibit mutagenic or clastogenic potential in a battery of assays including the Ames test, human peripheral lymphocyte chromosome aberration test, or the in vivo rat micronucleus test.
Reproductive and Developmental Toxicity
Fertility and early embryonic development were evaluated in rats. Pasireotide was administered by s.c. injection at 0.1, 1.0 and 10 mg/kg/day prior to mating, during mating, and through gestation day (GD) 6. Reproductive effects were observed in females only and included prolonged estrus cycles/acyclicity at doses ≥ 1.0 mg/kg and decreased numbers of corpora lutea, implantation sites, and/or viable fetuses at all doses. A NOAEL for female fertility was not established (<0.1 mg/kg/day).
Embryo-fetal development was evaluated in rats and rabbits. In rats, pasireotide was administered by s.c. injection at 1, 5, and 10 mg/kg/day from GD 6-17. At 10 mg/kg, and in the presence of maternal toxicity and mortality, effects on the F1 generation were noted and consisted of increased early/total resorptions, decreased fetal weights, and mal-rotated limbs. The fetal NOAEL was 5 mg/kg. Pasireotide was not teratogenic in the rat.
In rabbits, pasireotide was administered by s.c. injection at 0.05, 1.0 and 5.0 mg/kg/day from GD 7-20. Maternal toxicity was observed from 1.0 mg/kg and mortality occurred at 5.0 mg/kg. Reproductive and fetal effects (increased early and/or total resorptions, decreased fetal weights) were noted in the presence of maternal toxicity at doses ≥ 1 mg/kg. At 5 mg/kg, abortions and a decreased number of viable fetuses were seen. Increased skeletal variations noted at 5.0 mg/kg were considered secondary to the reduced fetal weights. The maternal and fetal NOAEL were 0.05 mg/kg. Pasireotide was not teratogenic in the rabbit.
Pre- and post-natal development were evaluated in rats. Pasireotide was administered by s.c. injection at 2, 5, and 10 mg/kg/day to F0 generation dams from GD 6 to day 21, 22, or 23 post partum. Maternal toxicity was observed at all doses and drug-related mortality was noted at 5 mg/kg. Maternal performance was unaffected by administration of pasireotide (no change in gestation index, length of gestation, numbers of live, dead pups, number of implantation scars, sex ratio and the live birth index). Lower F1 body weights were seen at all doses. Secondary to the lower pup weights, the mean day of pinna unfolding was slightly increased in all dose groups. Post weaning, body weight gains were comparable for all groups demonstrating reversibility. There was no effect on visual function, physical development, behavioural performance, macroscopic findings, parental performance or uterine findings for the F1 generation adults.
Special Toxicology
Antigenicity
Antigenicity was not evaluated with the s.c. formulation. Using pasireotide LAR in a rat i.m. study, anti-pasireotide antibodies were detected in 26/59 treated animals. The antibodies were considered non-neutralizing, as pharmacologic effects and drug levels were sustained.
Immunotoxicity
The immunotoxic potential of pasireotide was evaluated in a 4-week rat s.c. immunotoxicity study (dose levels: 0.08, 0.24, and 0.8 mg/kg/day). Pasireotide exhibits low immunotoxic potential. Although a slight decrease in lymphocytes counts was observed in males at 0.24 and 0.8 mg/kg/day (total lymphocyte counts and absolute counts of Total T lymphocytes, Helper T lymphocytes, Cytotoxic T lymphocytes, natural killer lymphocytes and B lymphocytes), there were no toxicologically-relevant pasireotide effects on immune function (anti‑KLH IgM, anti‑KLH IgG responses unaffected by pasireotide treatment).
Phototoxicity
In the absorption spectrum of pasireotide, a significant peak was found at around 360 nm. An in vitro phototoxicity assay was performed. Pasireotide did not exhibit phototoxic potential.