


Product Monograph - Sandoz Brimonidine / Timolol
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 08/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Test | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Ophthalmologic | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Peri-Operative Considerations | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Respiratory | 08/2023 |
| 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance | 08/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 5
4.5 Missed Dose ............................................................................................................. 5
5 OVERDOSAGE ............................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 7
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations ................................................................................................ 10
7.1.1 Pregnant Women ............................................................................................. 10
7.1.2 Breast-feeding .................................................................................................. 10
7.1.3 Pediatrics .......................................................................................................... 11
7.1.4 Geriatrics .......................................................................................................... 11
8 ADVERSE REACTIONS............................................................................................... 11
8.1 Adverse Reaction Overview ................................................................................... 11
8.2 Clinical Trial Adverse Reactions ............................................................................. 11
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 13
8.5 Post-Market Adverse Reactions ............................................................................. 13
9 DRUG INTERACTIONS .............................................................................................. 15
9.2 Drug Interactions Overview ................................................................................... 15
9.3 Drug-Behavioural Interactions ............................................................................... 16
9.4 Drug-Drug Interactions .......................................................................................... 16
9.5 Drug-Food Interactions .......................................................................................... 17
9.6 Drug-Herb Interactions .......................................................................................... 17
9.7 Drug-Laboratory Test Interactions......................................................................... 17
10 CLINICAL PHARMACOLOGY ...................................................................................... 17
10.1 Mechanism of Action ....................................................................................... 17
10.2 Pharmacodynamics .......................................................................................... 18
10.3 Pharmacokinetics ............................................................................................. 19
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 20
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 20
PART II: SCIENTIFIC INFORMATION ..................................................................................... 21
13 PHARMACEUTICAL INFORMATION .......................................................................... 21
14 CLINICAL TRIALS ...................................................................................................... 23
14.1 Trial Design and Study Demographics ............................................................. 23
Control of Intraocular Pressure ....................................................................................... 23
15 MICROBIOLOGY ...................................................................................................... 27
16 NON-CLINICAL TOXICOLOGY .................................................................................... 27
17 SUPPORTING PRODUCT MONOGRAPHS ........................................................................ 32
PATIENT MEDICATION INFORMATION ................................................................................ 32
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Sandoz Brimonidine / Timolol (brimonidine tartrate 0.2%/timolol as timolol maleate 0.5%) ophthalmic solution is indicated for:
- the control of intraocular pressure (IOP) in patients with chronic open-angle glaucoma or ocular hypertension who are insufficiently responsive to IOP reducing monotherapy AND when the use of Sandoz Brimonidine / Timolol is considered appropriate.
- reduction of long term fluctuation in IOP. In addition to controlling IOP, Sandoz Brimonidine / Timolol reduces long term variability, or fluctuation, in IOP. Together, reductions in IOP and in IOP fluctuation are expected to slow the progression of visual field loss in patients with glaucoma.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): Based on evidence from clinical studies and experience, use in the geriatric population is not associated with any differences in safety or effectiveness. Use as is for adult patients.
2 CONTRAINDICATIONS
NOTE: Sandoz Brimonidine / Timolol is a combination of brimonidine tartrate 0.2% and timolol 0.5% as timolol maleate. When Sandoz Brimonidine / Timolol is prescribed, the relevant Product Monographs for brimonidine tartrate and/or timolol maleate should be consulted.
- Patients who are hypersensitive to brimonidine tartrate, timolol maleate or to any ingredient in the formulation, including any non-medicinal ingredient or components of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with reactive airway disease including bronchial asthma or a history of bronchial asthma; severe chronic obstructive pulmonary disease
- Patients with sinus bradycardia; sick sinus syndrome; sino-atrial nodal block; second- or third-degree atrioventricular block not controlled with a pacemaker; overt cardiac failure; cardiogenic shock
- Patients receiving monoamine oxidase (MAO) inhibitor therapy
- Neonates and infants (children under the age of 2 years). See 8.5 Post-Market Adverse Reactions, brimonidine tartrate.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Diabetic patients: Beta-adrenergic blocking agents should be administered with caution in patients subject to spontaneous hypoglycaemia or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycaemia agents. See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism for considerations during use in this population.
- Patients should be advised that if they have ocular surgery or develop any type of ocular condition, they should immediately seek their doctor's advice concerning the continued use of the present bottle.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose is one drop of Sandoz Brimonidine / Timolol in the affected eye(s) twice daily (doses taken approximately 12 hours apart).
Health Canada has not authorized an indication for pediatric use.
4.4 Administration
As with any eye drops, it is recommended that the lachrymal sac be compressed at the medial canthus (punctual occlusion) for one minute, to reduce possible systemic absorption. This should be performed immediately following the instillation of each drop.
If more than one topical ophthalmic product is to be used, the different products should be instilled at least 10 minutes apart.
The preservative in Sandoz Brimonidine / Timolol, benzalkonium chloride, may be absorbed by and cause discoloration of soft (hydrophilic) contact lenses. Patients wearing soft contact lenses should be instructed to wait at least 15 minutes after instilling Sandoz Brimonidine / Timolol to insert soft contact lenses.
Patients should be instructed to avoid allowing the tip of the dispensing container to contact the eye or surrounding structures to avoid eye injury and contamination of eye drops. If handled improperly, ocular solutions can become contaminated by common bacteria known to cause ocular infections. Serious damage to the eye and subsequent loss of vision may result from using contaminated solutions.
4.5 Missed Dose
A missed dose should be applied as soon as the patient remembers. The regular dosing schedule should then be resumed with the next dose.
5 OVERDOSAGE
There is limited data available of overdosage in humans with the use of brimonidine tartrate / timolol maleate ophthalmic solution. Bradycardia has been reported in association with use of a higher than recommended dose. If overdosage occurs, treatment should be symptomatic and supportive; a patent airway should be maintained.
There have been reports of inadvertent overdoses with timolol maleate ophthalmic solution resulting in systemic effects similar to those seen with systemic beta-adrenergic blocking agents such as dizziness, headache, shortness of breath, bradycardia, bronchospasm, cardiac arrest.
There is very limited information regarding accidental ingestion of brimonidine in adults. The only adverse event reported to date was hypotension.
Treatment of an oral overdose includes supportive and symptomatic therapy; a patent airway should be maintained. Evacuation of the stomach should be considered during the first few hours after an overdose.
A study of patients with renal failure showed that timolol maleate did not dialyze readily.
Specific therapeutic measures for the treatment of overdose with timolol maleate are reproduced below for ease of reference:
- Gastric Lavage: If ingested.
- Symptomatic bradycardia: Use atropine sulfate intravenously in a dosage of 0.25 to 2 mg to induce vagal blockade. If bradycardia persists, intravenous isoproterenol hydrochloride should be administered cautiously. In refractory cases the use of a transvenous cardiac pacemaker may be considered.
- Hypotension: Use sympathomimetic pressor drug therapy, such as dopamine, dobutamine or levarterenol. In refractory cases the use of glucagon hydrochloride has been reported to be useful.
- Bronchospasm: Use isoproterenol hydrochloride. Additional therapy with aminophylline may be considered.
- Acute cardiac failure: Conventional therapy with digitalis, diuretics and oxygen should be instituted immediately. In refractory cases the use of intravenous aminophylline is suggested. This may be followed if necessary by glucagon hydrochloride which has been reported to be useful.
- Heart block (second or third degree): Use isoproterenol hydrochloride or a transvenous cardiac pacemaker.
| For management of a suspected drug overdose, including accidental oral ingestion, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Description
Sandoz Brimonidine / Timolol is a sterile solution and is supplied in white, opaque plastic dropper bottles containing: 5 mL or 10 mL.
7 WARNINGS AND PRECAUTIONS
General
NOTE: Sandoz Brimonidine / Timolol is a combination of brimonidine tartrate 0.2% and timolol 0.5% as timolol maleate. When Sandoz Brimonidine / Timolol is prescribed, the relevant Product Monographs for brimonidine tartrate and/or timolol maleate should be consulted.
FOR TOPICAL OPHTHALMIC USE ONLY.
If signs of serious reactions or hypersensitivity occur, discontinue use of this preparation.
As with many topically applied ophthalmic drugs, the active substances (brimonidine tartrate and timolol) in Sandoz Brimonidine / Timolol may be absorbed systemically. The same adverse reactions found with systemic administration of beta-adrenergic blocking agents may occur with topical administration of Sandoz Brimonidine / Timolol. For example, severe respiratory reactions and cardiac reactions, including death due to bronchospasm in patients with asthma, and rarely death in association with cardiac failure, have been reported following systemic or ophthalmic administration of timolol maleate. See 2 CONTRAINDICATIONS.
Carcinogenesis and Mutagenesis
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Ophthalmic | Solution, 0.2% brimonidine tartrate/timolol 0.5% as timolol maleate | Contains 0.005% benzalkonium chloride as preservative, dibasic sodium phosphate heptahydrate, monobasic sodium phosphate monohydrate; water for injection. Hydrochloric acid and/or sodium hydroxide may be added to adjust pH. |
See 16 NON-CLINIAL TOXICOLOGY
Cardiovascular
Because of the timolol maleate component, cardiac failure should be adequately controlled before beginning therapy with Sandoz Brimonidine / Timolol. In patients with a history of severe cardiac disease, coronary heart disease, Prinzmetal’s angina, signs of cardiac failure should be watched for and pulse rates should be checked.
Due to its negative effect on conduction time, beta-blockers should only be given with caution to patients with first degree heart block.
Caution should be exercised in treating patients with severe cardiovascular disease.
Use with caution in patients with cerebral or coronary insufficiency, Raynaud’s phenomenon, orthostatic hypotension or thromboangiitis obliterans.
Because of potential effects of beta-adrenergic blocking agents on blood pressure and pulse, these agents should be used with caution in patients with cerebrovascular insufficiency. If signs or symptoms suggesting reduced cerebral blood flow develop following initiation of therapy with Sandoz Brimonidine / Timolol alternative therapy should be considered.
Driving and Operating Machinery
Sandoz Brimonidine / Timolol, as with other similar medications, can potentially cause fatigue and/or drowsiness in some patients. Patients who engage in hazardous activities should be cautioned of the potential for a decrease in mental alertness. Sandoz Brimonidine / Timolol may also cause blurred vision or visual disturbance upon instillation. The patient should wait until these symptoms have cleared before driving or using machinery.
Endocrine and Metabolism
Beta-adrenergic blocking agents should be administered with caution in patients subject to spontaneous hypoglycaemia or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycaemia agents. Beta-adrenergic receptor blocking agents may mask the signs and symptoms of acute hypoglycaemia.
Beta-adrenergic blocking agents may mask certain clinical signs of hyperthyroidism (e.g., tachycardia). Patients suspected of developing thyrotoxicosis should be managed carefully to avoid abrupt withdrawal of beta-adrenergic blocking agents that might precipitate a thyroid storm.
Hepatic/Biliary/Pancreatic
Brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%has not been studied in patients with hepatic impairment; caution should be exercised in treating such patients.
Monitoring and Laboratory Tests
Patients prescribed IOP-lowering medication should be routinely monitored for IOP.
In clinical trials, abnormal liver function tests were noted. See 8.4 Abnormal Laboratory Findings:
Hematologic, Clinical Chemistry and Other Quantitative Data.
Musculoskeletal
Beta-adrenergic blockade has been reported to increase muscle weakness consistent with certain myasthenic symptoms (e.g., diplopia, ptosis and generalized weakness). Timolol maleate has been reported rarely to increase muscle weakness in some patients with myasthenia gravis or myasthenic symptoms.
Ophthalmologic
Sandoz Brimonidine / Timolol should not be used alone in the treatment of acute angle-closure glaucoma.
Choroidal detachment after filtration procedures has been reported with administration of aqueous suppressant therapy (e.g., timolol maleate, acetazolamide). Management of eyes with chronic or recurrent choroidal detachment should include stopping all forms of aqueous suppressant therapy and treating endogenous inflammation vigorously.
There have been reports of bacterial keratitis associated with the use of multiple dose containers of topical ophthalmic products. These containers had been inadvertently contaminated by patients who, in most cases, had a concurrent corneal disease or a disruption of the ocular epithelial surface.
Corneal diseases: Ophthalmic beta-blockers may induce dryness of eyes. Patients with corneal diseases should be treated with caution.
Peri-Operative Considerations
The necessity or desirability of withdrawal of beta-adrenergic blocking agents prior to major surgery is controversial. If necessary during surgery, the effects of beta-adrenergic blocking agents may be reversed by sufficient doses of such agonists as isoproterenol, dopamine, dobutamine or levarterenol.
Ophthalmic beta-blockers may impair compensatory tachycardia and increase risk of hypotension when used in conjunction with anesthetics. The anesthetist must be informed if the patient is using
Sandoz Brimonidine / Timolol.
Psychiatric
Sandoz Brimonidine / Timolol should be used with caution in patients with depression.
Renal
Brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% has not been studied in patients with renal impairment; caution should be exercised in treating such patients.
Respiratory
Patients with chronic obstructive pulmonary disease of mild or moderate severity should, in general, not receive products containing beta-blockers, including Sandoz Brimonidine / Timolol; however, if Sandoz Brimonidine / Timolol is deemed necessary in such patients, it should be administered with caution.
Sensitivity/Resistance
Because of the brimonidine tartrate component Sandoz Brimonidine / Timolol should be used with caution in patients with known hypersensitivity to other alpha-adrenoceptor agonists.
Delayed ocular hypersensitivity reactions have been reported with brimonidine tartrate ophthalmic solution 0.2%, with some reported to be associated with an increase in IOP.
While taking beta-blockers, patients with a history of atopy or a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated accidental, diagnostic, or therapeutic challenge with such allergens. These patients may be unresponsive to the usual doses of epinephrine used to treat anaphylactic reactions since timolol maleate may blunt the beta agonist effect of epinephrine. In such cases, alternatives to epinephrine should be considered.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies of Brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% ophthalmic solution in pregnant women. Because animal reproduction studies are not always predictive of human response, Sandoz Brimonidine / Timolol should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus.
There has been no experience with exposure during pregnancy in clinical trials.
7.1.2 Breast-feeding
Timolol maleate has been detected in human milk following oral and ophthalmic drug administration. It is not known whether brimonidine tartrate is excreted in human milk, although in animal studies, brimonidine tartrate has been shown to be excreted in breast milk. Because of the potential for serious adverse reactions from timolol maleate or brimonidine tartrate in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The use of Sandoz Brimonidine / Timolol in pediatric patients is currently not recommended. See 2 CONTRAINDICATIONS.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Based on evidence from clinical studies and experience, use in the geriatric population is not associated with any differences in safety or effectiveness. Use as is for adult patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Based on 12-month clinical data, the most commonly reported adverse drug reactions were conjunctival hyperaemia (approximately 15% of patients) and burning sensation in the eye (approximately 11% of patients). The majority of cases were mild and led to discontinuation rates of only 3.4% and 0.5% respectively.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In clinical trials, brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% ophthalmic solution was safe and well tolerated and had an acceptable safety profile. No adverse reactions unique to the combination product have been observed. All adverse reactions have been previously reported for brimonidine tartrate 0.2% or timolol 0.5% as timolol maleate, though at different incidences.
In two clinical studies including 385 patients treated with brimonidine tartrate / timolol maleate for up to 12 months, treatment-related adverse reactions reported (pooled analysis) occurring at ≥1% with brimonidine tartrate / timolol maleate ophthalmic solution are presented in Table 2 below.
Table 2: Treatment Related Adverse Reactions Occurring at ≥ 1% with brimonidine tartrate / timolol maleate ophthalmic solution
Combination n = 385 | Brimonidine Tartrate n = 382 | Timolol Maleate n = 392 | |
General disorders and administration site conditions asthenia | 8 (2.1%) | 16 (4.2%) | 3 (0.8%) |
Gastrointestinal disorders oral dryness | 8 (2.1%) | 35 (9.2%)a | 2 (0.5%) |
Nervous system disorders somnolence headache | 6 (1.6%) 4 (1.0%) | 14 (3.7%) 13 (3.4%)a | 2 (0.5%) 4 (1.0%) |
Eye disorders conjunctival hyperaemia burning sensation in eye stinging sensation eye eye pruritus allergic conjunctivitis conjunctival folliculosis visual disturbance (blurred vision) epiphora eye dryness superficial punctate keratitis erythema eyelid blepharitis eye discharge eyelid edema corneal erosion eye pain irritation eye foreign body sensation eyelids pruritus | 56 (14.5%) 42 (10.9%) 24 (6.2%) 21 (5.5%) 20 (5.2%) 19 (4.9%) 14 (3.6%) 12 (3.1%) 12 (3.1%) 12 (3.1%) 11 (2.9%) 11 (2.9%) 10 (2.6%) 10 (2.6%) 10 (2.6%) 6 (1.6%) 6 (1.6%) 5 (1.3%) 4 (1.0%) | 87 (22.8%)a 28 (7.3%) 11 (2.9%)b 42 (11.0%)a 36 (9.4%)a 35 (9.2%)a 16 (4.2%) 19 (5.0%) 13 (3.4%) 5 (1.3%) 12 (3.1%) 11 (2.9%) 7 (1.8%) 6 (1.6%) 5 (1.3%) 10 (2.6%) 3 (0.8%) 17 (4.5%)a 3 (0.8%) | 29 (7.4%)b 53 (13.5%) 26 (6.6%) 11 (2.8%) 1 (0.3%)b 7 (1.8%)b 12 (3.1%) 5 (1.3%) 4 (1.0%)b 4 (1.0%)b 4 (1.0%) 2 (0.5%)b 3 (0.8%)b 2 (0.5%)b 11 (2.8%) 6 (1.5%) 5 (1.3%) 7 (1.8%) 0 (0.0%) |
Psychiatric disorders depression | 4 (1.0%) | 3 (0.8%) | 1 (0.3%) |
Combination n = 385 | Brimonidine Tartrate n = 382 | Timolol Maleate n = 392 | ||||
Vascular disorders hypertension | 4 (1.0%) | 1 (0.3%) | 1 (0.3%) | |||
a incidence with the Combination was significantly lower than with monotherapy (p ≤ 0.05) b incidence with the Combination was significantly higher than with monotherapy (p ≤ 0.05) | ||||||
8.3 Less Common Clinical Trial Adverse Reactions
Cardiac disorders: congestive heart failure, palpitations
Eye disorders: visual acuity worsened, conjunctival oedema, follicular conjunctivitis, allergic blepharitis, conjunctivitis, vitreous floater, asthenopia, photophobia, papillary hypertrophy, eyelid pain, conjunctival blanching, corneal oedema, corneal infiltrates, vitreous detachment
Gastrointestinal disorders: taste perversion, diarrhea, nausea.
Nervous system disorders: dizziness, syncope
Respiratory, thoracic and mediastinal disorders: rhinitis, nasal dryness
Skin and subcutaneous tissue disorders: allergic contact dermatitis
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Common: Liver function tests abnormal
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-marketing use of brimonidine tartrate/timolol maleate ophthalmic solution in clinical practice. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
Cardiac disorders: bradycardia
Skin and subcutaneous tissue disorders: erythema facial
Additional adverse events that have been reported with one of the components and may be potential adverse reactions for brimonidine tartrate / timolol maleate ophthalmic solution are:
Brimonidine tartrate:
Adverse events reported in ≥ 1% and < 8% of patients receiving brimonidine tartrate, ophthalmic solution 0.2% include: Dizziness, upper respiratory symptoms, gastrointestinal symptoms, abnormal taste, nasal dryness, photophobia, tearing, conjunctival edema, conjunctival blanching, conjunctival papillae, and abnormal vision, tachycardia, hypersensitivity, skin reaction (including erythema, face edema, pruritus, rash, and vasodilatation).
In a 3-month, phase 3 study in children aged 2-7 years with glaucoma, inadequately controlled by betablockers, a high prevalence of somnolence (55%) was reported with brimonidine tartrate as adjunctive treatment. In 8% of children, this was severe and led to discontinuation of treatment in 13%. The incidence of somnolence decreased with increasing age, being least in the 7-year-old age group (25%), but was more affected by weight, occurring more frequently in those children weighing ≤ 20 kg (63%) compared to those weighing > 20 kg (25%).
The safety and effectiveness of brimonidine tartrate ophthalmic solution has not been studied in children under the age of two years. During post-marketing surveillance somnolence, lethargy, hypotonia, hypothermia, bradycardia, hypotension, apnoea, respiratory depression, pallor and coma have been reported in neonates, infants and children receiving brimonidine either for congenital glaucoma or via accidental ingestion.
For other detailed information, please consult the Product Monograph for brimonidine tartrate.
Timolol maleate:
Adverse events reported with timolol maleate include:
Cardiac disorders: Aggravation or precipitation of certain cardiovascular, pulmonary, and other disorders presumably related to effects of systemic beta blockade (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS, Cardiovascular), including bradycardia; arrhythmia; heart block; atrioventricular block; cerebrovascular accident; cerebral ischemia; palpitations; chest pain; cardiac arrest; edema; congestive heart failure, cardiac failure; pulmonary oedema; worsening of angina pectoris.
Ear and labyrinth disorders: tinnitus
Eye disorders: decreased corneal sensitivity; visual disturbances including refractive changes (due to withdrawal of miotic therapy in some cases); diplopia; ptosis; choroidal detachment following filtration surgery; refractive changes, conjunctivitis; blepharitis; keratitis; vision blurred.
Gastrointestinal disorders: nausea; diarrhea, dyspepsia; abdominal pain; dysgeusia; vomiting; dry mouth.
General disorders and administration site conditions: fatigue
Immune system disorders: signs and symptoms of allergic reactions including anaphylaxis, angioedema, localized and generalized rash, pruritus, urticaria; systemic lupus erythematous, hypersensitivity.
Metabolism and nutrition disorders: masked symptoms of hypoglycaemia in insulin-dependent diabetics
Musculoskeletal and connective tissue disorders: myalgia
Nervous system disorders: increase in signs and symptoms of myasthenia gravis; paresthesia; syncope; cerebrovascular accident; cerebral ischemia; dizziness and headache
Psychiatric disorders: insomnia, memory loss, nightmares, depression
Reproductive system and breast disorders: decreased libido; Peyronie’s disease, sexual dysfunction
Respiratory, thoracic and mediastinal disorders: bronchospasm (predominantly in patients with preexisting bronchospastic disease); respiratory failure; dyspnea; cough; upper respiratory infection
Skin and subcutaneous tissue disorders: alopecia; psoriasiform rash or exacerbation of psoriasis; skin rash
Vascular disorders: claudication; cold hands and feet; hypotension; Raynaud’s phenomenon
Causal Relationship Unknown:
The following adverse reactions have been reported but a causal relationship to therapy with timolol maleate has not been established: aphakic cystoid macular edema, nasal congestion, anorexia, central nervous system (CNS) effects (e.g., behavioral changes including confusion, hallucinations, anxiety, disorientation, nervousness, somnolence, and other psychic disturbances), hypertension, retroperitoneal fibrosis and pseudo pemphigoid.
Timolol maleate (systemic formulation):
Adverse reactions reported in clinical experience with oral timolol maleate may be considered potential side effects of ophthalmic timolol maleate.
Clinically important changes in standard laboratory parameters were rarely associated with the administration of systemic timolol maleate. Slight increases in blood urea nitrogen, serum potassium and serum uric acid and triglycerides, and slight decreases in hemoglobin and hematocrit and HDL-cholesterol occurred but were not progressive or associated with clinical manifestations.
For other detailed information, please consult the Product Monograph for timolol maleate.
9 DRUG INTERACTIONS
9.1 Drug Interactions Overview
No interaction studies have been performed with brimonidine tartrate / timolol maleate ophthalmic solution.
9.2 Drug-Behavioural Interactions
Although specific drug interaction studies have not been conducted with brimonidine tartrate / timolol maleate ophthalmic solution, the possibility of an additive or potentiating effect with CNS depressants such as alcohol exists.
9.3 Drug-Drug Interactions
Table 3 - Summary of Effect of Co-administered Drugs on Exposure to Brimonidine Tartrate / Timolol Maleate Ophthalmic Solution
| Co-administered drug | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Beta-adrenergic blockers | T | Potential additive effects of beta-blockade, both systemically and on intraocular pressure. | Concomitant use of two topical beta-adrenergic blocking agents is not recommended. |
Anti-hypertensives/cardiac glycosides (oral calcium channel blockers, antiarrhythmics (including amiodarone), digitalis glycosides, parasympathomimetics, guanethidine, and other anti-hypertensives) | T | Potential for additive effects resulting in hypotension, and/or marked bradycardia | No specific dosing adjustment is recommended. |
CNS depressants (alcohol, barbiturates, opiates, sedatives, or anesthetics) | T | Possibility of an additive or potentiating effect | Potential effects should be considered. |
| Tricyclic Antidepressants | T | Tricyclic antidepressants have been reported to blunt the hypotensive effect of systemic clonidine. It is not known whether the concurrent use of these agents with Brimonidine Tartrate / Timolol Maleate can lead to an interference in IOP lowering effect. | No data are available on the level of circulating catecholamines after Brimonidine Tartrate / Timolol Maleate ophthalmic solution is instilled. Caution, however, is advised in patients taking tricyclic antidepressants which can affect the metabolism and uptake of circulating amines. |
| Legend: T = Theoretical | |||
Table 4 – Summary of Effect of Co-administered Drugs on Exposure to Timolol Maleate
| Co-administered drug | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Clonidine | T | Oral beta-adrenergic blocking agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. | There have been no reports of exacerbation of rebound hypertension with ophthalmic timolol maleate. |
| Epinephrine | T | Mydriasis | No specific dosing adjustment is recommended. |
| Quinidine | T | Potentiated systemic beta-blockade (e.g., decreased heart rate) | Concomitant use of Brimonidine Tartrate / Timolol Maleate ophthalmic solution with Quinidine may inhibit the metabolism of timolol maleate via the P- 450 enzyme, CYP2D6. |
| Legend: T = Theoretical | |||
9.4 Drug-Food Interactions
Interactions with food have not been established.
9.5 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.6 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Brimonidine tartrate 0.2% / timolol as timolol maleate 0.5% ophthalmic solution reduces intraocular pressure (IOP) by reducing aqueous humor production and increasing uveoscleral outflow.
Sandoz Brimonidine / Timolol is a combination product containing brimonidine tartrate and timolol maleate. Individually, each of these components is used to control IOP in humans.
Brimonidine tartrate is a relatively selective alpha adrenergic receptor agonist that in radioligand binding assays and in functional assays, is approximately 1000 times more selective for the alpha-2 adrenoceptor than the alpha-1 adrenoceptor. This selectivity results in the absence of vasoconstriction in microvessels associated with human retinal xenografts.
Fluorophotometric studies in animals and humans suggest that brimonidine tartrate has a dual mechanism of action. Brimonidine tartrate lowers IOP by reducing aqueous humor production and increasing uveoscleral outflow.
Timolol maleate is a general beta-adrenergic receptor blocking agent that combines reversibly with a part of the cell membrane, the beta-adrenergic receptor, and thus inhibits the usual biological response that would occur with stimulation of that receptor. This specific competitive antagonism blocks stimulation of the beta-adrenergic receptors by catecholamines having beta-adrenergic stimulating (agonist) activity, whether these originate from an endogenous or exogenous source. Reversal of this blockade can be accomplished by increasing the concentration of agonist, which will restore the usual biologic response.
The precise mechanism of action of timolol maleate in lowering intraocular pressure is not clearly established at this time, although a fluorescein study and tonography studies indicate that its predominant action may be related to reduced aqueous humor formation.
Both brimonidine tartrate and timolol maleate have a rapid onset of action, with the peak ocular hypotensive effect occurring at approximately two hours post-dosing for brimonidine tartrate and one to two hours for timolol maleate. The duration of effect is 12 hours or greater for brimonidine tartrate and 24 hours for timolol maleate.
10.2 Pharmacodynamics
The topical administration of brimonidine tartrate 0.2% ophthalmic solution decreases intraocular pressure (IOP) with minimal effect on cardiovascular parameters. Brimonidine tartrate 0.2% has no effect on pulmonary function or exercise-induced tachycardia. The cardiovascular effects of brimonidine tartrate 0.2% during exercise in normal volunteers were found to be limited to a slight suppression of systolic blood pressure, which was clinically insignificant, during the recovery period following a treadmill test.
Timolol maleate is a non-cardioselective beta-adrenergic receptor blocking agent that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity.
Elevated IOP presents a major risk factor in glaucomatous visual field loss. The higher the level of IOP, the greater the likelihood of optic nerve damage and visual field loss. Fluctuation in IOP is related to the progression of glaucoma, with each 1 mm increase in IOP fluctuation raising the odds of progression in visual field loss by up to 30%. Timolol maleate ophthalmic solution 0.5%, a non-selective beta-blocker lowers IOP by decreasing aqueous humor production. Brimonidine tartrate ophthalmic solution 0.2%, a selective and potent alpha-2 adrenoceptor agonist, reduces IOP through reduction of aqueous humor production and an increase in nonpressure-dependent uveoscleral outflow. Brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% is a combination product containing brimonidine tartrate 0.2% and timolol 0.5% as timolol maleate.
10.3 Pharmacokinetics
Table 5 - Summary of brimonidine and timolol Pharmacokinetic Parameters in healthy subjects dosed with brimonidine tartrate/timolol maleate ophthalmic solution
Cmax (ng/mL) | Tmax (hr) | t½ (hr) | AUC0-12h (ng·hr/mL) | ||||||
| Brimonidine | |||||||||
BID for 7 days mean | 0.0327 | 1.28 | 2.43 | 0.128 | |||||
| Timolol | |||||||||
BID for 7 days mean | 0.406 | 2.42 | 7.32 | 2.92 | |||||
| Legend: BID= twice daily | |||||||||
Absorption:
Plasma brimonidine tartrate and timolol maleate concentrations were determined in 16 healthy subjects dosed with brimonidine tartrate 0.2% / timolol as timolol maleate 0.5%, brimonidine tartrate ophthalmic solution 0.2%, or timolol maleate ophthalmic solution USP 0.5%, each BID for seven days in a three-period, complete crossover study. There were no statistically significant differences in brimonidine tartrate or timolol maleate AUC between brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% and the respective monotherapy treatments. Mean plasma brimonidine tartrate Cmax values from the brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% and brimonidine tartrate 0.2% groups were 0.0327 ± 0.0150 (N = 15) and 0.0347 ± 0.0226 ng/mL (N = 16), respectively, indicating no apparent difference. Mean plasma timolol maleate Cmax values from the brimonidine tartrate 0.2% / timolol as timolol maleate 0.5% and timolol maleate USP 0.5% treatment groups were 0.406 ± 0.216 (N = 15) and 0.507 ± 0.269 ng/mL (N = 14), respectively. Although the Cmax of timolol maleate was approximately 20% lower in the brimonidine tartrate 0.2% / timolol as timolol maleate 0.5% ophthalmic solution treatment, the difference was not statistically significant (p=0.088).
Therapeutic drug monitoring was conducted in the two Phase 3 trials. Brimonidine tartrate and timolol maleate plasma concentrations from the brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% BID group were 15-49% lower than their respective monotherapy values. In the case of brimonidine tartrate, the difference appears to be due to BID dosing for the brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% and TID dosing for brimonidine tartrate 0.2% ophthalmic solution.
The lower timolol maleate plasma concentrations seen with brimonidine tartrate 0.2% / timolol as timolol maleate 0.5%, as compared to timolol maleate 0.5%, appear to be related to a slower absorption of timolol maleate, which may be due to a difference in the benzalkonium concentrations rather than a drug-drug (brimonidine tartrate-timolol maleate) interaction.
Orally administered timolol maleate is rapidly and nearly completely absorbed (~90% availability). The apparent elimination half-life of timolol maleate in plasma is 4 hours. The half-life is essentially unchanged in patients with moderate renal insufficiency.
These results on systemic absorption of topical drug from brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% versus monotherapy treatments are consistent with the more favourable safety profile demonstrated by the brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% treatment, as compared to brimonidine tartrate 0.2% ophthalmic solution TID and timolol maleate BID.
Metabolism:
Timolol maleate is partially metabolized by the liver and timolol maleate and its metabolites are excreted by the kidney. Timolol maleate is not extensively bound to plasma proteins (~ 60%). After oral dosing, timolol maleate is subject to moderate first-pass metabolism (~50%). Only a small amount of unchanged drug appears in the urine, along with its metabolites after oral dosing.
Elimination:
In humans, brimonidine tartrate is eliminated rapidly via extensive systemic metabolism; there is no marked systemic accumulation after multiple dosing. It is metabolized primarily by the liver. Urinary excretion is the major route of elimination of the drug and its metabolites. Approximately 87% of an orally-administered radioactive dose was eliminated within 120 hours, with 74% found in the urine in the first 96 hours.
11 STORAGE, STABILITY AND DISPOSAL
Sandoz Brimonidine / Timolol (brimonidine tartrate 0.2%/timolol as timolol maleate 0.5%) ophthalmic solution should be stored at room temperature (15°C to 25°C). Protect from light. Discard unused portion after 28 days from initial use.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Patients should be advised to avoid touching the tip of the bottle to the eye or any surface, as this may contaminate the solution. Refer to 4.4 Administration for more detailed information.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
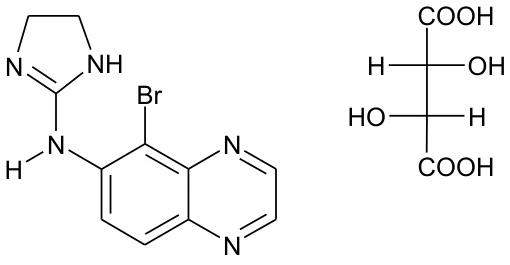
Brimonidine Tartrate
Proper name: brimonidine tartrate
Chemical name: 5-Bromo-6-(2-imidazolin-2-ylamino) quinoxaline L-tartrate
Molecular formula and molecular mass: C11H10BrN5 •C4H6O6 ; 442.24 g/mol
Structural formula:
Physicochemical properties: Brimonidine tartrate is a white to yellowish crystalline powder. It is freely soluble in water and insoluble in almost all organic solvents., with a melting point range of 208 to 212oC. The pH in water is 3 to 4 at room temperature.
Timolol Maleate
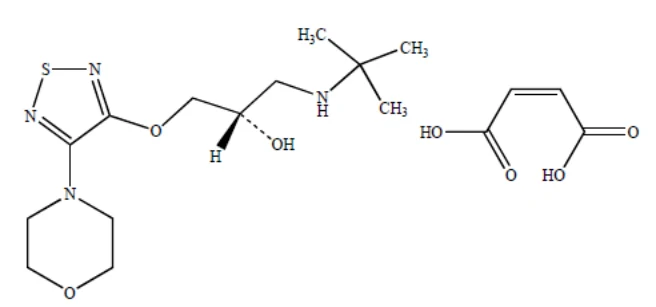
Proper name: timolol maleate
Chemical name: 2-Propanol, 1-(1,1-dimethylethyl)amino-3-[[4-(4-morpholinyl)-1,2,5-thiadiazol-3-yl]oxy]-, (S)-, (Z)-2-butenedioate (1:1) (salt)
Molecular formula and molecular mass: C13H24N4O3S • C4H4O4
316.4 g/mol (Timolol Base) and
432.50 g/mol (Timolol Maleate)
Structural formula:
Physicochemical properties: Timolol maleate is a white or pratically white, odourless or pratically odourless crystalline powder, which is soluble in water, methanol and ethanol. Timolol maleate is optically active. The specific rotation is between -11.7º and -12.5º (λ= 405 nm). Test solution: 50 mg per mL, in 1.0 N hydrochloric acid and has a melting point of 199°C.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Control of Intraocular Pressure
Table 6 - Summary of patient demographics for clinical trials in the control of intraocular pressure
| Study # | Study design | Dosage, route of administration and duration | Subjects (n) | Mean age (Range) | Sex |
| 190342-012T | Randomized, Double-blind, Parallel Group, Active Control | One drop in each affected eye. Brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%: BID Timolol maleate 0.5%:BID Brimonidine tartrate 0.2%: TID Ocular 12 Months | 573 enrolled 192 195 186 (497 completed 3 mo; 407 completed 12 mo) | 62.8 years (32 to 89) | M: 43.3 % (248/573) F: 56.7% (325/573) |
| 190342-013T | Randomized, Double-blind, Parallel Group, Active Control | One drop in each affected eye. Brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%: BID Timolol maleate 0.5%: BID Brimonidine tartrate 0.2%: TID Ocular 12 Months | 586 enrolled 193 197 196 (502 completed 3 mo; 426 completed 12 mo) | 62.4 years (23 to 87) | M: 46.1% (270/586) F: 53.9% (316/586) |
Three clinical trials evaluating the safety and efficacy of brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% ophthalmic solution in the treatment of patients with glaucoma or ocular hypertension have been performed.
A phase 2 study (N=73) was conducted to evaluate the safety, efficacy and tolerability of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% dosed twice-daily, compared with brimonidine tartrate 0.2% dosed three-times-daily and timolol maleate 0.5% dosed twice-daily, each administered for 7 days. The study demonstrated that the short-term dosing with brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% was well tolerated with a safety profile similar to timolol maleate and to brimonidine tartrate, and provided statistically significant and clinically relevant reduction of IOP of up to 7.8 mm Hg from baseline in patients with glaucoma or ocular hypertension.
Two 12-month clinical studies (N=1159) were conducted to determine the efficacy and safety of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% ophthalmic solution administered BID compared with brimonidine tartrate 0.2% administered TID and timolol maleate 0.5% administered BID in patients with glaucoma or ocular hypertension.
The study population included adult subjects diagnosed with ocular hypertension, chronic open-angle glaucoma, chronic angle-closure glaucoma with a patent iridotomy, pseudoexfoliative glaucoma, or pigmentary glaucoma. Primary inclusion criteria were post-washout morning IOP (Baseline, Hour 0) of at least 22 mm Hg and no higher than 34 mm Hg in each eye, asymmetry of IOP not greater than 5 mm Hg, and best-corrected Early Treatment of Diabetic Retinopathy Study (ETDRS) visual acuity equivalent to a Snellen score of 20/100 or better in each eye.
Study results
During the 12-month treatment period, the greater IOP lowering effect of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% BID was demonstrated throughout the day, and this effect was maintained during the 12 months treatment period. Furthermore, analysis of the long-term safety data showed that brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% had an acceptable safety profile, and that adverse experiences were limited to those that were reported previously with brimonidine tartrate ophthalmic solution 0.2% and/or timolol maleate ophthalmic solution 0.5%.
The efficacy results (pooled analysis) from the two 12 month clinical trials are presented in Table 7 below:
Table 7 - Results of Studies -012T and -013T in the control of intraocular pressure
| Primary Endpoints | Statistical significance for Brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% versus Brimonidine Tartrate | Statistical significance for Brimonidine tartrate 0.2% / timolol maleate as timolol 0.5% versus Timolol Maleate |
| Mean IOP (hours 0, 2, 7, and 9) at Weeks 2, 6, Months 3, 6, 9, (Hours 0 and 2 only), Month 12; pooled data from Studies 190342-012T and 190342-013T | Mean IOP was significantly lower with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% than with brimonidine tartrate TID at Hours 0, 2, 7, and 9 at all follow-up visits (p ≤ 0.018) except for Week 2, Hour 9 (p=0.093) | Mean IOP was significantly lower with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% than with timolol maleate at hours 0, 2, 7, and 9 at all follow-up visits (p < 0.001) |
Supplemental analyses of pooled Studies 190342-012T and 190342-013T demonstrated that brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% was clinically and statistically more effective both in lowering IOP and in stabilizing IOP fluctuation than either brimonidine tartrate administered TID or timolol maleate administered BID.
Table 8 - Proportion of Patients with Daily IOP SD Fluctuation Less Than 3 mmHg and Mean IOP Less than 18 mmHg (Pooled 12-Month Studies 012T and 013T)
| Visit | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% N = 384 | Brimonidine Tartrate N = 381 | Timolol Maleate N = 392 | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% vs. Brim p-valuea | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% vs. Timolol p-valuea |
|---|---|---|---|---|---|
| Week 2 | 64.5% | 28.8% | 45.6% | <0.001 | <0.001 |
| Week 6 | 65.5% | 32.0% | 48.8% | <0.001 | <0.001 |
| Month 3 | 64.1% | 33.1% | 44.8% | <0.001 | <0.001 |
| Month 6 | 61.7% | 27.0% | 43.1% | <0.001 | <0.001 |
| Month 9 | 49.5% | 23.5% | 34.7% | <0.001 | <0.001 |
| Month 12 | 58.1% | 31.6% | 41.2% | <0.001 | <0.001 |
Note: Daily fluctuation is the standard deviation at the visit. Patients with complete data for the visit are included. Mean IOP is the mean diurnal IOP for the specified visit a P-value for the between-group comparison at each visit is based on Chi-Square | |||||
Table 9- Proportion of Patients with Hourly IOP SD Fluctuation Less Than 3 mmHg and Mean IOP
Less than 18 mmHg (Pooled 12-Month Studies 012T and 013T)
| Visit | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% N = 288 | Brimonidine Tartrate N = 213 | Timolol Maleate N = 327 | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% Vs. Brim p-valuea | Brimonidine Tartrate 0.2% /Timolol Maleate as timolol 0.5% Vs. Timolol p-valuea |
|---|---|---|---|---|---|
| Hour 0 | 145/288 (50.3%) | 32/213 (15.0%) | 112/325 (34.5%) | <0.001 | <0.001 |
| Hour 2 | 215/279 (77.1%) | 107/211 (50.7%) | 156/321 (48.6%) | <0.001 | <0.001 |
| Hour 7 | 177/281 (63.0%) | 70/207 (33.8%) | 160/322 (49.7%) | <0.001 | 0.001 |
| Hour 9 | 180/278 (64.7%) | 121/204 (59.3%) | 161/315 (51.1%) | 0.223 | <0.001 |
Note: Hourly fluctuation is the standard deviation at that hour across all visits. Patients with data at each visit for the given hour are included. Mean IOP is the mean of the IOPs at all visits for the specified hour. a P-value for the between-group comparison at each visit is based on Chi-Square | |||||
In a supplemental analysis of a subgroup of patients receiving systemic beta-blockers in the pooled studies, the mean change from baseline IOP was significantly lower (p < 0.001) with brimonidine tartrate 0.2% /timolol as timolol maleate 0.5% ophthalmic solution than with either brimonidine tartrate TID or timolol maleate administered BID. There was no statistically significant difference in IOP reduction between patients receiving beta blockers and those who were not for patients who were treated with brimonidine tartrate 0.2% /timolol as timolol maleate 0.5% ophthalmic solution (-6.2 mm Hg vs. -6.2 mm Hg, p = 0.920) or with brimonidine tartrate (-3.7 mm Hg vs. -4.1 mm Hg, p = 0.400). However, patients treated with timolol maleate who were also receiving concomitant systemic beta blockers had a significantly smaller reduction in IOP than those who were not treated with a concomitant beta-blocker (-3.8 mm Hg versus -4.9 mm Hg, p = 0.007).
A supplemental analysis of a subgroup of diabetic and non-diabetic patients was also performed on the pooled data. Mean change from baseline IOP with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% was significantly lower (p < 0.001) with than either brimonidine tartrate or timolol maleate for both diabetics and non-diabetics. For patients with diabetes mellitus, there was no statistically significant difference in IOP reduction from baseline in comparison to non-diabetic patients following treatment with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% (-5.9 mm Hg vs. -6.3 mm Hg, p = 0.241). With brimonidine tartrate treatment however, diabetic patients had a significantly smaller IOP reduction effect than non-diabetics (-3.3 mm Hg vs. -4.2 mm Hg, p = 0.003). Similarly, with timolol maleate treatment, diabetic patients had a significantly smaller effect than non-diabetics (-4.1 mm Hg vs. -5.0 mm Hg, p = 0.004).
In the Phase 3 studies, heart rate was measured at pre-study, baseline, and each follow-up visit at Hour 0 (pre-dose) and Hour 2 (post-dose). In each study, small but statistically significant mean decreases from baseline with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5%were similar to those with timolol maleate. Mean decreases were significantly greater with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% than with brimonidine tartrate at Hour 2 for each follow-up visit in each study.
Systolic and diastolic blood pressure were measured at prestudy, baseline, and each follow-up visit at hour 0 (pre-dose) and hour 2 (post-dose). At hour 0 in each study, small within-group changes from baseline systolic blood pressure were generally not significant. At Hour 2, small but statistically significant mean decreases from baseline with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% were similar to those with brimonidine tartrate. There were no statistically significant differences between brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% and either individual component in the mean change from baseline systolic blood pressure at any time point in either study.
At Hour 0 in each study, small within-group changes from baseline diastolic blood pressure were generally not significant. At Hour 2, small but statistically significant mean decreases from baseline with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% were similar to those with brimonidine tartrate. Mean decreases at Hour 2 were significantly greater with brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% than with timolol maleate at each follow-up visit in each study. Generally, the differences in mean decrease in diastolic blood pressure between the brimonidine tartrate 0.2% /timolol maleate as timolol 0.5% and brimonidine tartrate groups were not significant.
Diabetics:
Results from pivotal trials indicate that the mean change from baseline IOP was significantly lower (p < 0.001) with brimonidine tartrate/timolol maleate than with either brimonidine tartrate alone or timolol maleate alone for both patients with diabetes and those without diabetes.
Patients using Systemic Beta-blockers:
Results from pivotal trials indicate that the mean change from baseline IOP was significantly lower (p < 0.001) with brimonidine tartrate/timolol maleate than with either brimonidine tartrate alone or timolol maleate alone for both patients treated with systemic beta blockers and those who were not. Topical beta-blockers are known to be less effective in patients on systemic beta-blockers. See 9 DRUG INTERACTIONS. This analysis shows that this is not the case with brimonidine tartrate/timolol maleate, despite having timolol as one of the ingredients.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity:
The acute median lethal dose (LD50) or minimum lethal dose (MLD) values of brimonidine tartrate were evaluated in mice, rats, rabbits, and dogs by oral and intravenous (i.v.) administration. The LD50 or MLD values for each study are listed below:
| Species | Route | LD50 (mg/kg)* | MLD (mg/kg)* |
|---|---|---|---|
| Mouse | oral i.v.* | 50 50 | > 8 ** Not performed |
| Rat | oral i.v. | 100 100-150 | > 8 ** Not performed |
| Rabbit | oral i.v. | Not performed Not performed | > 6 20-50 |
| Dog | oral i.v. | Not performed Not performed | 0.5 0.05 |
* The doses are expressed as the base except in the mouse and rat MLD data, where they are expressed as brimonidine tartrate. ** The data from additional single dose oral studies of 0.2% and 0.5% solutions of brimonidine tartrate in mice and rats showed that the oral MLD is greater than 10 mg/kg. | |||
The most frequently observed clinical signs in the acute/single dose toxicity studies were primarily due to the exaggerated pharmacological hypotensive effect of the compound. These signs included: sedation, ataxia, prostration, ptosis, reduced/loss of blink reflex, opacification of the cornea, hypotension, bradycardia, hypothermia, respiratory depression, respiratory arrest and circulatory collapse. The ocular changes were seen only after doses at or above the minimum lethal dose.
The oral LD50 of timolol maleate is 1190 mg/kg (3570 mg/m2) in female mice and 900 mg/kg (5310 mg/m2) in female rats.
Signs of toxicity including lacrimation, ataxia, tremors and bradypnea occurred immediately after intravenous administration and from 10 to 30 minutes following oral, intraperitoneal or subcutaneous administration. Clonic convulsions typically preceded death.
Long-term Toxicity
Brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% ophthalmic solution containing 50 ppm benzalkonium chloride was administered to New Zealand White rabbits as 1 drop in 1 eye 3 times daily for 6 months. Brimonidine tartrate 0.2% (alone), timolol maleate 0.5% (alone), and the vehicle for brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% were used as comparators. All formulations were well tolerated. No ocular irritation and no pathological findings were observed in ocular or systemic tissue. Transient, slight ocular discomfort was noted for all formulations, including the vehicle. Slight, transient (<3 hrs) sedation was noted in rabbits treated with brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% or brimonidine tartrate (alone). This effect is considered an exaggerated pharmacological effect of alpha-2-adrenergic receptor activation. Plasma Cmax and AUC daily exposure values, respectively, for brimonidine tartrate (43 and 14 times) or timolol maleate (15 and 4.5 times) were increased in the rabbit study above the similar values measured in humans treated with 1 drop of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% in both eyes 2 times per day.
Carcinogenicity:
In studies with brimonidine tartrate, there was no compound-related oncogenic effect observed in either mice or rats.
The maximal brimonidine tartrate plasma concentrations after oral administration of 2.5 mg base/kg/day to mice for 21 months correspond to approximately 150 times the human systemic exposure to brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% instilled in both eyes (one drop) twice daily. After two years of oral administration at 1.0 mg base/kg/day to rats, plasma Cmax concentrations were approximately 210 times greater than those seen in humans receiving one drop of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% in both eyes BID. There were no observable tumorigenic effects seen in mice or rats dosed at 2.5 mg base/kg/day or 1.0 mg base/kg/day, (approximately 150 times and 210 times the recommended human ocular dose), respectively.
In a two-year study of timolol maleate administered orally to rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (approximately 25000 times the human daily dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%). Similar differences were not observed in rats administered oral doses equivalent to approximately 8300 times the maximum recommended human ophthalmic dose.
In a lifetime oral study in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinomas in female mice at 500 mg/kg/day, (approximately 42000 times the human daily dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%), but not at 5 or 50 mg/kg/day (approximately 420 to 4200, respectively, times the human daily dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%). In a subsequent study in female mice, in which post-mortem examinations were limited to the uterus and the lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day.
The increased occurrence of mammary adenocarcinomas was associated with elevations in serum prolactin which occurred in female mice administered oral timolol maleate at 500 mg/kg/day, but not at doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents that elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in humans. Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate (the maximum recommended human oral dosage), there were no clinically meaningful changes in serum prolactin.
Genotoxicity:
Brimonidine tartrate was not mutagenic or cytogenetic in a series of in vitro and in vivo studies including the Ames/Salmonella mutagenicity assay, chromosomal aberration assay in Chinese Hamster Ovary (CHO) cells, cytogenetic assay, host-mediated assay and dominant lethal assay in mice.
Timolol maleate was negative for mutagenic potential when tested in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg/kg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL). In the Ames assays the highest concentrations of timolol maleate, 5000 or 10000 mcg/plate, were associated with statistically significant elevations of revertants with tester strain TA 100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA 100, no consistent dose response relationship was observed, and the ratio of test to control revertants was less than 2. A ratio of 2 is usually considered the criterion for a positive response with strain TA 100.
Reproductive and Developmental Toxicology:
Reproductive toxicology studies conducted with brimonidine tartrate in rats and rabbits showed that brimonidine tartrate had no adverse effects on fertility and general reproductive performance, and showed no evidence of embryolethality or teratogenicity at the dosages administered.
The mean maximal plasma brimonidine tartrate concentrations measured during the rat teratogenicity study (1.65 mg base/kg/day, orally) were approximately 600 times the maximum human systemic exposure to brimonidine tartrate 0.2%/timolol maleate as timolol 0.5% instilled in each eye (one drop) twice daily. Mean maximal plasma brimonidine concentrations in the rabbit teratogenicity study (3.33 mg base/kg/day, orally) were approximately 43 times greater than plasma concentrations seen in humans receiving one drop of brimonidine tartrate 0.2%/timolol as timolol maleate 0.5% in each eye BID.
There were no treatment-related reproductive and teratological effects observed in the F1 rat pup group, although a reduction in body weight was observed at a dose level of 1.65 mg base/kg/day, after 14 days. Dose related reduction in body weight gains were observed in rat dams at dose levels of 0.66 and 1.65 mg base/kg/day after 15 days.
Body weight loss, reduced food consumption, and spontaneous abortions occurred in two of eight rabbits at the 3.3 mg base/kg/day level (gestation day 21 or 23), and may have been the result of the exaggerated pharmacological effects observed at this level. No abortions occurred at the 0.165 or 0.66 mg base/kg/day level. Maternal necropsy was generally unremarkable. There was no evidence of treatment-related embryotoxicity, fetal toxicity, or teratogenicity at dosage levels up to 3.3 mg base/kg/day (approximately 825 times the recommended daily human ocular dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%. In another study involving 20 rabbit dams, dosed orally up to 2.64 mg base/kg/day, no adverse effects were observed other than a decrease in weight gain during the dosing period, and no treatment related embryolethal or teratogenic effects were observed.
Reproduction and fertility studies in rats with timolol maleate showed no adverse effect on male or female fertility at doses up to 4200 times the maximum recommended human ocular dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%.
Teratogenicity studies with timolol maleate in mice, rats, and rabbits at oral doses up to 50 mg/kg/day (4200 times the daily human dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%) demonstrated no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring. Doses of 1000 mg/kg/day (83000 times the daily human dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 8300 times higher than the maximum recommended human ophthalmic dose of brimonidine tartrate 0.2%/timolol maleate as timolol 0.5%, in this case without apparent maternotoxicity.
17 SUPORTING PRODUCT MONOGRAPHS
- 1. PrCOMBIGAN® ophthalmic solution, brimonidine tartrate 0.2% w/v and timolol 0.5% w/v (as timolol maleate), submission control: 267372, Product Monograph, AbbVie Corporation. (OCT 3, 2022)