


Product Monograph - Sandoz Doxycycline
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
|---|---|---|
| Oral | Modified-release capsule / 40 mg | None. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING section. |
INDICATIONS AND CLINICAL USE
Sandoz Doxycycline (doxycycline modified-release capsules) is indicated for the treatment of only inflammatory lesions (papules and pustules) of rosacea in adult patients. No meaningful effect was demonstrated for generalized erythema (redness) of rosacea.
Sandoz Doxycycline contains an antibacterial ingredient, doxycycline. Misuse or overuse of Sandoz Doxycycline could lead to the development of drug-resistant bacteria. To reduce the development of drug-resistant bacteria and maintain the effectiveness of doxycycline, Sandoz Doxycycline should only be used for the authorized indication and clinical use.
Pediatrics (<18 years of age):
Safety and efficacy in children below the age of 18 years have not been established.
Geriatrics (≥ 65 years of age):
Clinical studies of doxycycline modified-release capsules did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
CONTRAINDICATIONS
Sandoz Doxycycline (doxycycline monohydrate) modified-release capsule is contraindicated in
- patients who are hypersensitive to this drug, to other tetracyclines, or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section.
- women in the second or third trimester of pregnancy, or nursing women
- infants and children up to the age of 8 years
- patients with myasthenia gravis
(see WARNINGS AND PRECAUTIONS).
WARNINGS AND PRECAUTIONS
General
Sandoz Doxycycline (doxycycline monohydrate) modified-release capsules contain doxycycline in a formulation designed to yield plasma levels below the antimicrobial threshold. Sandoz Doxycycline should not be used for treating bacterial infections, providing antibacterial prophylaxis, or reducing the numbers or eliminating microorganisms associated with any bacterial disease.
Use of doxycycline with other drugs and food:
Use of doxycycline with other drugs or food may lead to drug-drug or drug-food interactions (see DRUG INTERACTIONS).
Concurrent use of an oral retinoid and doxycycline should be avoided due to reports of pseudotumor cerebri (see DRUG INTERACTIONS).
Carcinogenesis and Mutagenesis
Doxycycline hyclate was evaluated in a long-term animal study. Increases in benign tumours of the mammary gland (fibroadenoma), uterus (polyp) and thyroid (C-cell adenoma) were noted in female rats. Evidence of oncogenic activity was obtained in studies with related compounds, i.e., oxytetracycline (adrenal and pituitary tumors) and minocycline (thyroid tumors).
Data from an in vitro assay with Chinese hamster ovary (CHO) cells for potential to cause chromosomal aberrations suggest that doxycycline hyclate is a weak clastogen (see
TOXICOLOGY).
Gastrointestinal
Sandoz Doxycycline is not recommended in patients with gastrectomy, gastric bypass surgery, or any surgeries that bypass or exclude the duodenum, or who are otherwise deemed achlorhydric (see ACTION AND CLINICAL PHARMACOLOGY).
Clostridium difficile-associated disease:
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including doxycycline. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents. In the event of the development of diarrhea during treatment with Sandoz Doxycycline, the possibility of pseudomembranous colitis should be considered and appropriate therapy instituted. This may include the discontinuation of Sandoz Doxycycline.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Esophagitis/Esophageal ulceration:
Rare instances of esophagitis and esophageal ulcerations have been reported in patients receiving solid oral dosage forms of tetracyclines. Most of the patients experiencing esophagitis and/or esophageal ulceration took their medication immediately before lying down. Administration of adequate amounts of fluid along with the capsule is recommended to wash down the capsule to reduce the risk of esophageal irritation and ulceration (see Dosage and Administration).
Hepatic/Biliary/Pancreatic
Caution should be exercised when administering Sandoz Doxycycline to patients with hepatic impairment or to those receiving potentially hepatotoxic medicinal products. Doxycycline blood levels in patients treated with doxycycline modified-release capsules are lower than in those treated with conventional antimicrobial formulations of doxycycline. However, there are no data to support safety in hepatic impairment at this lower dose.
Immune
Hypersensitivity:
There have been isolated reports of hypersensitivity reactions in clinical trials. If an allergic reaction occurs, administration of Sandoz Doxycycline should be discontinued at once and appropriate emergency therapy should be initiated.
Autoimmune disorders:
Autoimmune syndromes, including drug-induced lupus-like syndrome, autoimmune hepatitis, vasculitis and serum sickness have been associated with tetracycline-class antibiotics.
Symptoms may be manifested by arthralgia, fever, rash and malaise. In symptomatic patients, liver function tests, ANA, CBC, and other appropriate tests should be performed to evaluate the patient. Use of all tetracycline-class drugs should be discontinued immediately.
Musculoskeletal
Use of Sandoz Doxycycline is contraindicated in patients with myasthenia gravis due to the risk of worsening of the myasthenia gravis condition.
Neurological
Pseudotumor cerebri (benign intracranial hypertension) in adults has been associated with the use of tetracyclines. The usual clinical manifestations are headache and blurred vision. Bulging fontanels have been associated with the use of tetracyclines in infants. While both of these conditions and related symptoms usually resolve after discontinuation of the tetracycline, the possibility for permanent sequelae exists. Patients should be questioned for visual disturbances prior to initiation of treatment with Sandoz Doxycycline and should be routinely checked for papilledema while on treatment.
Ophthalmologic
Sandoz Doxycycline should not be used in patients with ocular manifestations of rosacea (such as ocular rosacea and/or blepharitis/meibomianitis) as this patient population was not studied in clinical trials.
Renal
The anti-anabolic action of tetracyclines may cause an increase in BUN. Studies indicate that this anti-anabolic effect does not occur with the use of doxycycline in patients with impaired renal function.
Sensitivity/Resistance
Bacterial resistance to tetracyclines may develop in patients using Sandoz Doxycycline. Due to the potential for drug-resistant bacteria to develop during the use of Sandoz Doxycycline, it should only be used as indicated (see MICROBIOLOGY).
Sexual Function/Reproduction
The effect of doxycycline modified-release capsules on human fertility is unknown. However, oral administration of doxycycline hyclate adversely affected fertility and reproductive performance in rats (see TOXICOLOGY).
Skin
Photosensitivity:
Photosensitivity manifested by an exaggerated sunburn reaction has been observed in some individuals taking tetracyclines. Although this was not observed during clinical studies with doxycycline modified-release capsules, patients should minimize or avoid sun exposure or exposure to artificial sunlight (tanning beds or UVA/B treatment) while using Sandoz Doxycycline and should discontinue therapy at the first sign of phototoxicity/skin erythema. The use of sunscreen and other sun protection measures should be considered by patients taking Sandoz Doxycycline.
Tissue Hyperpigmentation:
Tetracycline class antibiotics are known to cause hyperpigmentation in many organs. Skin and oral pigmentation has been reported to occur independently of time or amount of drug administration, whereas other pigmentation has been reported to occur upon prolonged administration.
Special Populations
The use of drugs of the tetracycline class during tooth development (second and third trimester of pregnancy, infancy, and childhood up to the age of 8 years) may cause permanent discolouration of the teeth (yellow-grey-brown). This adverse reaction is more common during long-term use of the drug but has been observed following repeated short-term courses. Enamel hypoplasia has also been reported. Tetracycline drugs, therefore should not be used during tooth development.
All tetracyclines form a stable calcium complex in any bone-forming tissue. A decrease in fibula growth rate has been observed in premature human infants given oral tetracycline in doses of 25 mg/kg every 6 hours. This reaction was shown to be reversible when the drug was discontinued.
Results of animal studies indicate that tetracyclines cross the placenta, are found in fetal tissues and can cause retardation of skeletal development on the developing fetus. Evidence of embryotoxicity has been noted in animals treated in early pregnancy.
Pregnant Women:
Sandoz Doxycycline should not be used during pregnancy. Doxycycline, like other tetracycline-class antibiotics, can cause fetal harm when administered to a pregnant woman. If any tetracycline is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patients should be apprised of the potential hazard to the fetus.
Use of Sandoz Doxycycline is contraindicated in the second and third trimester of pregnancy when the teeth are developing.
Nursing Women:
Use of Sandoz Doxycycline is contraindicated in women while they are breastfeeding due to the risk of dental discolouration and decreased bone growth in the infant. Low levels of tetracyclines are excreted in the milk of nursing women.
Pediatrics (<18 years of age):
The safety and efficacy of doxycycline modified-release capsules in children below the age of 18 years have not been studied and therefore use in children is not recommended.
Use of Sandoz Doxycycline is contraindicated in infancy and childhood up to the age of 8 years due to the risk of dental discolouration and decreased bone growth.
Monitoring and Laboratory Tests
In therapy with doxycycline, periodic laboratory evaluations of organ systems, including hematopoietic, renal and hepatic studies should be performed.
Susceptibility/Resistance
Development of Drug Resistant Bacteria
Prescribing Sandoz Doxycycline in the absence of the authorized indications is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Potential for Microbial Overgrowth
As with other antibiotics, use of Sandoz Doxycycline may result in overgrowth of non-susceptible microorganisms, including fungi. If superinfection occurs, Sandoz Doxycycline should be discontinued and appropriate therapy instituted.
Although not observed in clinical trials with doxycycline modified-release capsules, the use of tetracyclines may increase the incidence of vaginal candidiasis. Sandoz Doxycycline should be used with caution in patients with a history of or predisposition to candidiasis overgrowth.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The total number of patients experiencing adverse reactions in clinical trials was 56 (20.8%) for the doxycycline modified-release capsule treatment group (N = 269) and 38 (14.2%) for the placebo group (N = 268).
The most frequently reported adverse reactions in the doxycycline modified-release capsule treatment group in Phase III studies were diarrhea (4.1%), headache (2.2%), abdominal pain upper (1.9%), fungal infection (1.9%), nausea (1.9%), aspartate aminotransferase increased (1.5%) and stomach discomfort (1.1%). Most adverse reactions were mild or moderate in severity. Only 4.8% of patients treated with doxycycline modified-release capsules discontinued due to an adverse reaction. The most frequent adverse reaction leading to discontinuation was diarrhea (0.7%).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In two controlled clinical trials of adult patients with rosacea, 537 patients received doxycycline modified-release capsules or placebo over a 16-week period. The adverse reactions assessed by the Investigator as probably or possibly related and reported in at least 1% of the patients treated with doxycycline modified-release capsules in the Phase III studies are listed in Table 1 below.
Table 1 - Adverse Reactions Reported in Phase III Clinical Trials by ≥ 1% of doxycycline modified-release capsule-treated Patients (16 Weeks)
| System Organ Class / Preferred Term | Doxycycline Modified-Release Capsules (N = 269) n (%) | Placebo (N = 268) n (%) |
|---|
Gastrointestinal Diarrhea Nausea Abdominal pain, upper Stomach discomfort | 11 (4.1) 5 (1.9) 5 (1.9) 3 (1.1) | 4 (1.5) 8 (3.0)
|
|---|---|---|
Nervous system Headache | 6 (2.2) | 11 (4.1) |
Infections and infestations Fungal infection | 5 (1.9) | 1 (0.4) |
Investigations AST increased | 4 (1.5) | 0 |
AST = Aspartate aminotransferase
Less Common Clinical Trial Adverse Drug Reactions (<1%)
The following less common adverse events have been designated by the Investigator as related (possible, probable) to treatment with doxycycline modified-release capsules in clinical trials.
Blood and lymphatic: Anemia.
Cardiovascular: Ventricular extrasystoles, palpitations.
Ear and labyrinth: Vertigo.
Eye: Photophobia.
Gastrointestinal: Dyspepsia (heartburn), gastrointestinal discomfort, gastrointestinal pain, gastroesophageal reflux disease, gastritis, vomiting, abdominal discomfort, abdominal pain, abdominal distension, constipation, dysphagia, loose stool, dry mouth.
General disorders: Malaise, chest pain, aches.
Immune: Bronchospasm, facial edema.
Infections and infestations: Candidiasis, vaginal candidiasis, furuncle (boil), cystitis, upper respiratory tract infection, influenza, bronchitis.
Injury and poisoning: Sunburn, laceration.
Investigations: Liver function tests abnormal, alanine aminotransferase increased, blood lactate dehydrogenase increased, weight gain, blood uric acid increase, blood pressure increased.
Metabolism and nutrition: Anorexia.
Musculoskeletal and connective tissue: Muscle cramp, muscle spasm.
Nervous system: Balance disorder, dysgeusia, dizziness, ageusia.
Psychiatric: Depression, anxiety, insomnia.
Renal and urinary tract: Micturition urgency.
Reproductive: Vaginal discharge.
Respiratory, thoracic and mediastinal: Dyspnoea, pharyngolaryngeal pain, asthma. Skin and subcutaneous tissue: Pruritus, skin burning sensation, dry skin, rash, rosacea, dermatitis, skin reaction.
Post-Market Adverse Drug Reactions
The following events have been reported since the global launch of doxycycline modified-release capsules. These events have been chosen for inclusion due to either their seriousness and/or frequency of reporting. Post-market adverse reactions are reported spontaneously from a population of unknown size, thus estimates of frequency cannot be made.
Blood and lymphatic: Anemia hemolytic autoimmune, leucopenia.
Cardiovascular: Tachycardia, arrhythmia.
Eye disorders: Blurred vision, diplopia.
Gastrointestinal: Large intestine perforation, esophageal ulcer, pancreatis.
Infections and infestations: Pseudomembranous colitis, clostridium difficile colitis, clostridial infection.
Investigations: Increased blood bilirubin, liver function tests abnormal. Musculoskeletal and connective tissue: Myalgia.
Nervous system: Migraine, benign intracranial hypertension, headache.
Skin and subcutaneous tissue: Photosensitivity reaction.
Vascular disorders: Vasculitis necrotising.
Adverse Reactions for Tetracyclines
The following adverse reactions have been observed in patients receiving tetracyclines at higher, antimicrobial doses:
Blood: hemolytic anemia, thrombocytopenia, neutropenia, and eosinophilia have been reported.
Ear and labyrinth: tinnitus
Gastrointestinal: anorexia, nausea, vomiting, diarrhea, glossitis, dysphagia, enterocolitis, and inflammatory lesions (with vaginal candidiasis) in the anogenital region. Rare instances of esophagitis and esophageal ulcerations have been reported in patients receiving the capsule forms of the drugs in the tetracycline class. Most of the patients experiencing esophagitis and/or esophageal ulceration took their medication immediately before lying down.
Hepatic: hepatotoxicity (including hepatic failure, autoimmune hepatitis and cholestasis), hepatitis (elevation of alanine amintransferase or aspartate aminotransferase values) have been reported.
Immune: urticaria, angioneurotic edema, anaphylaxis, anaphylactoid purpura, serum sickness, pericarditis, and exacerbation of systemic lupus erythematosus.
Musculoskeletal: arthralgia and myalgia.
Neurological: flushing, headache, bulging fontanels in infants, benign intracranial hypertension in adults.
Other: discolouration of the thyroid gland.
Renal toxicity: rise in BUN has been reported and is apparently dose-related (see WARNINGS
AND PRECAUTIONS).
Skin: maculopapular and erythematous rashes, photosensitivity skin reactions, photoonycholysis, erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis, exfoliative dermatitis have been reported.
DRUG INTERACTIONS
Drug-Drug Interactions
Drug-drug interaction studies with doxycycline modified-release capsules have not been conducted. The recommendations below regarding the potential interactions between doxycycline and other medications are based upon experience with higher doses of doxycycline generally used in antimicrobial formulations.
Absorption of tetracyclines including doxycycline may be inhibited by proton pump inhibitors , bi- and trivalent ions such as aluminum, calcium or magnesium (found for example in antacids, dairy products and calcium-containing fruit juices), or by iron-containing preparations, activated charcoal, chlolestryramine, bismuth chelates and sucralfate. Therefore, such medicines should be taken after a period of 2 to 3 hours following ingestion of Sandoz Doxycycline.
Quinapril may reduce the absorption of doxycycline due to the high magnesium content in quinapril tablets. Quinapril, therefore, should be taken after a period of 2 to 3 hours following ingestion of Sandoz Doxycycline.
Medicinal products which increase gastric pH may reduce the absorption of doxycycline. Rifampicin, barbiturates, carbamazepine, diphenylhydantoin, primidone, phenytoin and chronic alcohol abuse may accelerate the metabolism of doxycycline due to enzyme induction in the liver, thereby decreasing its half-life. Sub-therapeutic doxycycline concentrations may result.
Concurrent use of cyclosporin has also been reported to decrease the half-life of doxycycline. Consequently, there should be a 2 hours gap between the two treatments.
There have been reports of pseudotumor cerebri (benign intracranial hypertension) associated with the concomitant use of oral retinoids and tetracyclines. The concurrent use of an oral retinoid and doxycycline should therefore be avoided.
Bacteriostatic drugs including doxycycline may interfere with the bacteriocidal action of βlactam class antibiotics including penicillin. Concurrent use of β-lactam class antibiotics and doxycycline should be avoided.
Doxycycline has been shown to depress plasma prothrombin activity. If doxycycline is administered in combination with anticoagulants, coagulation parameters should be monitored and, if necessary those patients who are on anticoagulant therapy may require downward adjustment of their anticoagulant dosage.
Tetracyclines may interfere with the effectiveness of low dose oral contraceptives. To avoid contraceptive failure, a second form of contraceptive may be advised during treatment with doxycycline.
The concurrent use of tetracyclines and methoxyfluorane has been reported to result in fatal renal toxicity.
Doxycycline has been shown to potentiate the hypoglycemic effect of sulphonylurea oral antidiabetic agents. If administered in combination with these medicinal products, blood glucose levels should be monitored and, if necessary, the doses of the sulphonylureas should be reduced.
Drug-Food Interactions
The ingestion of food delayed and reduced the rate and extent of absorption of doxycycline modified-release capsules (see ACTION AND CLINICAL PHARMACOLOGY - Absorption).
This decrease in systemic exposure can be clinically significant, and therefore it is recommended that Sandoz Doxycycline be taken at least one hour prior to or two hours after the meal (see DOSAGE AND ADMINISTRATION - Recommended Dose and Dosage Adjustment).
The absorption of doxycycline may be inhibited by bi- or tri-valent ions such as aluminum, zinc, calcium (found for example in dairy products and calcium-containing fruit juices), therefore these foods should be taken 2 to 3 hours following ingestion of doxycycline.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
False elevations of urinary catecholamine levels may occur due to interference with the fluorescence test.
Drug-Lifestyle Interactions
All patients receiving doxycycline, including Sandoz Doxycycline, should be advised to minimize or avoid sunlight or artificial ultraviolet light (see WARNINGS AND PRECAUTIONS – Skin). Use of sunscreen or sunblock should be considered.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The dosage of Sandoz Doxycycline modified-release capsules differs from that of doxycycline used to treat infections. Exceeding the recommended dosage may result in an increased incidence of side effects including the development of resistant organisms.
Efficacy and safety of doxycycline modified-release capsules for the treatment of rosacea beyond 16 weeks have not been established.
Recommended Dose and Dosage Adjustment
One Sandoz Doxycycline capsule (40 mg, modified-release) should be taken once daily in the morning, on an empty stomach, preferably at least one hour prior to or two hours after the meal.
Administration
Administration of adequate amounts of fluid along with the capsule is recommended to wash down the Sandoz Doxycycline capsule to reduce the risk of esophageal irritation and ulceration (see WARNINGS AND PRECAUTIONS – Gastrointestinal).
Special Populations:
Pediatrics (<18 years of age):
Doxycycline modified-release capsules have not been evaluated in pediatric subjects. The use of doxycycline is contraindicated in children up to the age of 8 years due to the risk of dental discolouration and decreased bone growth. See section Special Warnings and Precautions for Use.
Gastric Insufficiency:
Sandoz Doxycycline is not recommended in patients with gastrectomy, gastric bypass surgery or any surgeries that bypass or exclude the duodenum, or who are otherwise deemed achlorhydric (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics).
Missed Dose
If a single dose of Sandoz Doxycycline is missed, that daily dose should be skipped and the patient should be instructed to take the next dose at the regular time.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
No cases of overdose have been reported during clinical trials with doxycycline modified-release capsules. In the case of overdosage, the medication should be discontinued immediately and the patient should be treated symptomatically. Dialysis does not alter doxycycline pharmacokinetics and therefore would not be of benefit in treating cases of overdose.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The pathophysiology of the inflammatory lesions of rosacea is, in part, a manifestation of a neutrophil-mediated process. Doxycycline has been shown to inhibit neutrophil activity and several pro-inflammatory reactions including those associated with phospholipase A2, endogenous nitric oxide and interleukin-6. The clinical significance of these findings is not known.
Pharmacokinetics
Doxycycline modified-release capsules are not bioequivalent to other doxycycline products. The pharmacokinetics of doxycycline following oral administration of doxycycline modified-release capsules was investigated in two studies involving 61 adults. Pharmacokinetic parameters for doxycycline modified-release capsules following single oral doses and at steady-state (7 consecutive days) in fasting healthy subjects are presented in Table 2 below.
Table 2 - Summary of Doxycycline Modified-Release Capsule Pharmacokinetic Parameters
| N | Cmax* (ng/mL) | Tmax ** (h) | AUC0-∞* (ng-hr/mL) | T1/2* (h) | |
|---|---|---|---|---|---|
| Single dose 40 mg modified-release capsule | 30 | 510 ± 220.7 | 3.00 (1.0-4.1) | 9227 ± 3212.8 | 21.2 ± 7.6 |
| Steady state*** 40 mg modified-release capsules | 31 | 600 ± 194.2 | 2.00 (1.0-4.0) | 7543 ± 2443.9 | 23.2 ± 6.2 |
*Mean ±SD, **Median (range), ***Day 7
The plasma concentration of doxycycline following administration of doxycycline modified-release capsules was well below the level required to inhibit microorganisms commonly associated with bacterial disease.
Absorption:
Doxycycline is almost completely absorbed after oral administration. In a single-dose food-effect study involving administration of doxycycline modified-release capsules to healthy volunteers, co-administration with a 1000 calorie, high-fat, high protein meal that included dairy products reduced the bioavailability (AUC) of doxycycline from doxycycline modified-release capsules by about 20% and reduced the peak plasma level by 43%, compared to dosing under fasted conditions.
Distribution:
No new distribution studies have been performed with doxycycline modified-release capsules since doxycycline is a well-established drug substance. Doxycycline is lipophilic and widely distributed in the tissues. The reported volume of distribution varies from 52.6 to 134 L. Information from the literature indicates that doxycycline is about 80-90% bound to plasma proteins.
Metabolism:
No new metabolism studies have been performed with doxycycline modified-release capsules since doxycycline is a well-established drug substance. Major metabolites of doxycycline have not been identified. However, enzyme inducers such as barbiturates, carbamazepine, and phenytoin decrease the half-life of doxycycline (for a comprehensive list of enzyme inducers, see DRUG INTERACTIONS - Drug-Drug Interactions).
Excretion:
Doxycycline is excreted in the urine and faeces as almost unmetabolized drug. Between 29-55% of an administered dose can be accounted for in the urine within 72 hours.
Special Populations and Conditions
Pediatrics (<18 years of age):
Pharmacokinetic studies have not been conducted in children 18 years old or younger.
Geriatrics (≥ 65 years of age):
Doxycycline pharmacokinetics have not been evaluated in geriatric patients.
Gender:
The pharmacokinetics of doxycycline modified-release capsules were compared in 16 male and 14 female subjects under fed and fasted conditions. Female subjects had a higher Cmax and AUC than male subjects, however a subgroup analysis by gender of the Phase 3 clinical studies did not show a gender difference in clinical outcome.
Renal Insufficiency:
Studies have shown no significant difference in serum half-life of doxycycline in patients with normal and severely impaired renal function. Hemodialysis does not alter the serum half-life of doxycycline.
Hepatic Insufficiency:
Doxycycline pharmacokinetics have not been evaluated in patients with hepatic insufficiency.
Gastric Insufficiency:
In a study in healthy volunteers (N=24) the bioavailability of doxycycline is reported to be reduced at high pH. This reduced bioavailability may be clinically significant in patients with gastrectomy, gastric bypass surgery or any surgeries that bypass or exclude the duodenum, or who are otherwise deemed achlorhydric.
STORAGE AND STABILITY
Sandoz Doxycycline should be stored at controlled room temperature (15°C to 30°C). Store in the original package to protect from light.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Sandoz Doxycycline are available as Opaque beige cap/ opaque beige body size '2' capsules with 'T42' imprinted with black ink on cap, containing yellow to greyish yellow colored and beige to greyish beige colored pellets.
The 40 mg capsule consists of immediate-release pellets equivalent to 30 mg (yellow to greyish yellow pellets) & delayed-release pellets equivalent to 10 mg (beige to greyish beige pellets).
The non-medicinal ingredients in Sandoz Doxycycline are hypromellose, methacrylic acid copolymer, Instacoat Universal Beige, sugar spheres, Simethicone emulsion, hard gelatin capsule shell, talc and triethyl citrate.
Sandoz Doxycycline is available as 10-capsule blister cards packaged in a carton of three cards (30 capsules).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | doxycycline monohydrate |
|---|---|
| Chemical name: | 2-Naphthacenecarboxamide,4-(dimethylamino)- 1,4,4a,5,5a,6,11,12a-octahydro- 3,5,10,12,12apentahydroxy-6-methyl-1,11-dioxo-, monohydrate,[4S-(4α, 4aα, 5α, 5aα, 6α, l2aα)] or α -6-deoxy-5-hydroxytetracycline Monohydrate |
| Molecular formula: | C22H24N2O8•H2O |
| Molecular mass: | 462.46 g/mol |
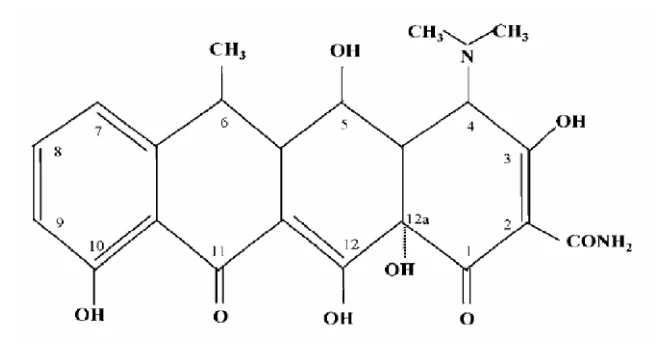
Structural formula:
| Physicochemical properties: | Doxycycline monohydrate is a yellow crystalline powder that dissolves in dilute solutions of mineral acids and in solutions of alkali hydroxides and carbonates. It is slightly soluble in methanol 1% 1M HC1, very slightly soluble in water and in alcohol, and practically insoluble in chloroform and in ether. |
|---|
CLINICAL TRIALS
Comparative Bioavailability Study:
Two studies have been conducted:
A single dose randomized, two-period, two-way crossover bioavailability study comparing Sandoz Doxycycline modified-release capsules, 40 mg (doxycycline monohydrate) (Sandoz Canada Incorporated) to APPRILON® modified-release capsules, 40 mg (doxycycline monohydrate) (Galderma Canada Incorporated) was conducted under fasting conditions in 24 healthy male adult subjects. The results are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Doxycycline (doxycycline monohydrate) (1 x 40 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-t (h*ng/mL) | 6483.21 6620.48 (20.01) | 6363.67 6507.77 (20.93) | 101.88 | 98.57 to 105.30 |
AUC0-inf (h*ng/mL) | 6674.87 6806.52 (19.40) | 6538.08 6683.58 (20.79) | 102.09 | 98.76% to 105.54 |
Cmax (ng/mL) | 406.13 421.83 (27.18) | 388.50 413.38 (36.28) | 104.54 | 97.90% to 111.63 |
| Tmax (h) ** | 3.00 (1.00, 4.50) | 2.750 (0.99, 4.49) | ||
| T½ el (h) § | 16.97 17.11 (12.91) | 16.36 16.57 (16.04) | ||
* Sandoz Doxycycline modified-release capsule, 40 mg (doxycycline monohydrate) (Sandoz Canada Incorporated).
† APPRILON® modified-release capsule, 40mg (doxycycline monohydrate) (Galderma Canada Incorporated) were purchased in Canada.
** Expressed as median (range) only
§ Expressed as the arithmetic mean (CV %) only.
A single dose randomized, two-period, two-way crossover bioavailability study comparing Sandoz Doxycycline modified-release capsules, 40 mg (doxycycline monohydrate) (Sandoz Canada Incorporated) to APPRILON® modified-release capsules, 40 mg (doxycycline monohydrate) (Galderma Canada Incorporated) was conducted under fed conditions in 23 healthy male adult subjects. The results are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Doxycycline (doxycycline monohydrate) (1 x 40 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-t (h*ng/mL) | 4983.03 5045.73 (15.83) | 4811.63 4880.05 (17.37) | 103.38 | 99.37 to 107.55 |
AUC0-inf (h*ng/mL) | 5175.28 5238.06(15.67) | 5021.59 5088.81 (16.89) | 102.92 | 98.90 to 107.10 |
Cmax (ng/mL) | 212.70 217.26 (20.93) | 211.41 217.96 (26.60) | 100.18 | 95.39 to 105.21 |
| Tmax (h)** | 4.498 (1.99, 10.05) | 4.495 (2.00, 10.00) | ||
| T½ el§ (h) | 17.15 17.44 (18.58) | 17.17 17.55 (21.07) | ||
* Sandoz Doxycycline modified-release capsule, 40 mg (doxycycline monohydrate) (Sandoz Canada Incorporated).
† APPRILON® modified-release capsule, 40mg (doxycycline monohydrate) (Galderma Canada Incorporated) were purchased in Canada.
** Expressed as median (range) only
§ Expressed as the arithmetic mean (CV %) only.
Study demographics and trial design
Table 3 - Summary of patient demographics and trial design for clinical trials in rosacea*
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (Total number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
301 (USA, 7 centers) | Randomized, double-blind, placebo-controlled, parallel-group study |
| (251) 127 doxycycline modified-release capsules 124 placebo | 47.2 years (19 – 90 years) | 65 male 186 female |
302 (USA, 7 centers) | Randomized, double-blind, placebo-controlled, parallel-group study. Treatment period was followed by a 4-week period off therapy to evaluate the persistence of treatment effect. |
| (286 on therapy) 142 doxycycline modified-release capsules 144 placebo (160 off therapy) 84 doxycycline modified-release capsules 76 placebo | 47.0 years (19 – 82 years) | 97 male 189 female |
|---|
*Study patients had rosacea (10 to 40 papules and pustules and ≤ 2 nodules)
Study results
The following table presents the primary endpoint, which is the mean change in total inflammatory lesion count from baseline to Week 16 (Table 4).
Table 4 - Study 301 and 302: Mean change in total inflammatory lesion count from baseline to Week 16 (ITT population)
| Study 301 | Study 302 | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Doxycycline Modified-Release Capsules (N = 127) | Placebo (N = 124) | Doxycycline Modified-Release Capsules (N = 142) | Placebo (N = 144) | |||||||||
| Baseline | ||||||||||||
| Mean (SD) | 19.5 (8.8) | 20.3 (10.4) | 20.5 (11.1) | 21.2 (12.5) | ||||||||
| Week 16a | ||||||||||||
| Mean (SD) | 7.7 (8.0) | 14.4 (16.4) | 11.0 (11.3) | 16.9 (14.7) | ||||||||
Change from baseline Mean (SD) | -11.8 (9.8) | -5.9 (13.9) | -9.5 (9.6) | -4.3 (11.6) | ||||||||
| p-Valueb | <0.001 | <0.001 | ||||||||||
SD = standard deviation
Total inflammatory lesion count included the number of papules, pustules and nodules.
aWeek 16 was the last valid observation available on treatment.
bp-Value for treatment difference for change from baseline, using the Van Elteren test stratified by pooled centre.
The following table provides the proportion of treatment responders at Week 16 (Table 5).
Table 5 - Study 301 and 302: Proportion of treatment respondersa at Week 16b (ITT population)
| Treatment response | Study 301 | Study 302 | ||||
|---|---|---|---|---|---|---|
Doxycycline modified-release capsules (N = 127) n (%) | Placebo (N = 124) n (%) | Doxycycline modified-release capsules (N = 142) n (%) | Placebo (N = 144) n (%) | |||
Clear or Near Clear | 39 (30.7%) | 24 (19.4%) | 21 (14.8%) | 9 (6.3%) | |||
|---|---|---|---|---|---|---|---|
| p-Value | 0.036 | 0.012 | |||||
| Clear | 12 (9.4%) | 10 (8.1%) | 2 (1.4%) | 14 (5.2%) | |||
| p-Valuec | 0.718 | 0.134 | |||||
aTreatment responder was a patient assessed as Clear or Near Clear (defined as one or two papules) at Week 16.
bWeek 16 was the last valid observation available on treatment.
cp-Value for treatment differences was based on a Cochran-Mantel-Haenszel test stratified by pooled centre.
Patients treated with doxycycline modified-release capsules did not demonstrate significant improvement in erythema when compared to those treated with placebo.
DETAILED PHARMACOLOGY
No new animal pharmacodynamic studies have been conducted with doxycycline modified-release capsules.
MICROBIOLOGY
Doxycycline is a member of the tetracycline class of antibiotics. The plasma concentration of doxycycline following administration of doxycycline modified-release capsules is below the level required to treat bacterial diseases. In vivo microbiological studies using immediate-release doxycycline (20 mg twice daily) for 6 to 18 months demonstrated no detectable effect on bacterial flora sampled from the oral cavity, skin, intestinal tract and vagina and did not reveal any evidence of increased bacterial resistance.
TOXICOLOGY
Toxicology studies included in this section were conducted with doxycycline hyclate (not doxycycline monohydrate).
Single-Dose Toxicity and Repeat-Dose Toxicity
Table 6 - An overview of single-dose and repeat-dose toxicological studies (conducted with doxycycline hyclate)
Species and Strain | Method of Administration | Duration of Dosing | Doses | Gender and No. per Group | Noteworthy Findings |
|---|---|---|---|---|---|
| Single-Dose Toxicity | |||||
Species and Strain | Method of Administration | Duration of Dosing | Doses | Gender and No. per Group | Noteworthy Findings |
|---|---|---|---|---|---|
Rat Crl:CD(SD)BR (VAF) Plus | Oral (gavage) | Single dose | 500, 750 mg/kg | MTD test (500 and 750 mg/kg): 2M, 2F Limit test (500 mg/kg): 5M, 5F | Administration of 750 mg/kg was associated with mortality (1 male at day 3); 500 mg/kg did not elicit any deaths or produce any apparent signs of toxicity. |
| Repeat-Dose Toxicity | |||||
Rat Crl:CD(SD)BR (VAF) plus | Oral (gavage) | 14 days | 0, 50, 100, 200, 400 mg/kg/day | 15M, 15F | All doses: hair loss 200: slight reduction in liver weights in males 400: post-dose salivation, food consumption slightly reduced in males, slight reduction in liver weights in males |
Rat Sprague Dawley | Oral (gavage) | 13 weeks | 0, 25, 100, 400, 600 mg/kg/day | 10M, 10F | Majority of findings were present at 400 and 600 mg/kg/day, however, there were some changes at all dose levels although the nature of these was minimal or slight at the lower doses. Findings were indicative of discomfort in the abdominal cavity (labored breathing, hunched posture, distended abdomen, subdued behaviour) and this was confirmed in the histopathological findings of the stomach. In one of the male and female early decedents, gastric erosions were found to be a contributing factor to death. Slight reductions were present in weight gain during the first month of the study and at the beginning of the study there was a reduction in food consumption in 400 and 600 mg/kg/day animals. Clinical pathology investigations showed a number of changes in 400 and 600 mg/kg/day animals and a reduction in protein at 25 mg/kg/day upwards. The changes in the red cell parameters may correlate with the apparent suppression of extramedullary hematopoiesis in the spleen which was also lighter in these animals. Terminal observations included decreased heart and spleen weights and increased kidney weights. Histopathological evaluation identified |
Species and Strain | Method of Administration | Duration of Dosing | Doses | Gender and No. per Group | Noteworthy Findings |
|---|---|---|---|---|---|
| thyroid and adrenal glands, spleen, stomach, duodenum and cecum as target organs. In the thyroid, brown pigment was presented at 25 mg/kg/day upwards. The stomach changes were present at 100 mg/kg/day upwards and at 25 mg/kg/day there was evidence of an increase of minimal submucosal inflammation. | |||||
Monkey Cynomolgus | Oral (gavage) | 4 weeks | 0, 5, 25, 50 mg/kg/day | 3M, 3F | Generally well tolerated and produced minimal signs of toxicity at all dose levels. Salivation and vomiting were seen in a few 25 mg/kg/day animals and more frequently in most of the 50 mg/kg/day animals. Histopathological evaluation revealed evidence of kidney lesions at 25 and 50 mg/kg/day. Urea levels were increased in 25 and 50 mg/kg/day animals. Terminal observations included decreased adrenal weights and increased kidney weights. Histopathology findings revealed a dose-related incidence and severity of tubular degeneration/regeneration and interstitial edema of the kidney and evidence of increased mucus production in the stomach. |
Monkey Cynomolgus | Oral (gavage) | 12 months | 0, 5, 15, 30 mg/kg/day | 4M, 4F | Generally well tolerated and produced minimal signs of toxicity at all dose levels. Salivation and/or vomiting during or immediately after dosing was seen in several animals from all 4 groups but more frequently in the 15 and 30 mg/kg/day groups. Histopathological examination revealed a dose-related increase in the incidence and severity of tubular degeneration/regeneration in the kidney, especially at 15 and 30 mg/kg/day. Dark thyroid gland was observed in 30 mg/kg/day animals. Interstitial edema in the kidneys was observed in 15 and 30 mg/kg/day animals. Brown pigment in the follicular epithelium of the thyroid was observed in 30 mg/kg/day animals. |
F: females; M: males; MTD: Maximum Tolerated Dose
The oral (dietary) administration of doxycycline at 50, 250 and 500 mg/kg/day for up to 18 months in rats resulted in a reduction in liver weight at 250 and 500 mg/kg/day and pigmentation of the thyroid gland at all dosages. Histopathology revealed that one rat in the 500 mg/kg dose group had multiple areas of stomach necrosis.
Subchronic oral administration of doxycycline in beagle dogs for up to 11 days at approximately 250 mg/kg/day was associated with marked toxicity. Post-mortem examination of the mortality indicated a toxic effect in the liver and stomach.
The oral (dietary) administration of doxycycline at 5, 25 or 50 mg/kg doxycycline for up to 12 months in rhesus monkeys was studied. No deaths occurred and no treatment-related changes were reported in haematology, blood chemistry or urinalysis parameters. Animals in the 50 mg/kg dose group showed fluorescence of bones and teeth under ultraviolet light. Macroscopic observation of the thyroids revealed brownish discolouration in one animal of the 50 mg/kg dose group and a similar finding was apparent in animals of the 25 mg/kg dose group.
Histopathological examination of the thyroids confirmed the presence of a brownish pigment in three animals of the 50 mg/kg dose group.
Genotoxicity
Doxycycline hyclate demonstrated no potential to cause genetic toxicity in an in vitro point mutation study with mammalian cells (CHO/HGPRT forward mutation assay) or in an in vivo micronucleus assay conducted in CD-1 mice. However, data from an in vitro assay with CHO cells for potential to cause chromosomal aberrations suggest that doxycycline hyclate is a weak clastogen.
Positive results in in vitro mammalian cell assays have been reported for related antibiotics (tetracycline, oxytetracycline).
Carcinogenicity
Doxycycline hyclate was assessed for potential to induce carcinogenesis in a study in which the compound was administered to Sprague-Dawley rats by gavage at dosages of 20, 75, and 200 mg/kg/day for two years. Increases in benign tumours of the mammary gland (fibroadenoma), uterus (polyp) and thyroid (C-cell adenoma) were noted in females.
Noteworthy non-neoplastic findings included brown pigment in the thyroid, observed in all treated groups. Reduction in bodyweight gain and cystic endometrial hyperplasia in the uterus was observed in females treated with 200 mg/kg/day. Focal epithelial hyperplasia in the stomach was observed in males and females treated with 200 mg/kg/day. Catarrhal exudate and inflammatory cell infiltrate/inflammation in the nasopharynx was observed in males and females treated with 75 and 200 mg/kg/day.
Evidence of oncogenic activity was obtained in studies with related compounds, i.e., oxytetracycline (adrenal and pituitary tumors) and minocycline (thyroid tumors).
Reproductive and Development Toxicity
In a fertility and reproductive study, five groups of 25 male and 25 female rats were dosed by oral gavage at dose levels of 0, 50, 100, 250 or 500 mg/kg/day doxycycline hyclate. A similar control group received purified water. The males were dosed for 28 days prior to mating, throughout the mating period and until the day before necropsy. The females were dosed for 14 days prior to mating, during the mating period and until day 7 of pregnancy. The study demonstrated that the oral administration of doxycycline hyclate to Sprague-Dawley rats adversely affected fertility and reproductive performance, as evidenced by increased time for mating to occur, reduced sperm motility, velocity, and concentration, abnormal sperm morphology, and increased pre-and post implantation losses. Doxycycline induced reproductive toxicity at all dosages in the study, as even the lowest dose tested (50 mg/kg per day) induced a statistically significant reduction in sperm velocity. Note that 50 mg/kg/day is approximately 3.6 times the amount of doxycycline contained in the recommended daily dose of doxycycline modified-release capsules for a 60-kg human when compared on the basis of area under the curve (AUC) estimates.
No embryo-fetal development study was performed with doxycycline. However, doxycycline is known to cross the placenta and literature data indicate that tetracyclines can have toxic effects on the developing fetus.
In a study for effects on prenatal and postnatal development, including maternal function, five groups of 25 pregnant female rats (F0 generation) were treated with doxycycline hyclate at dose-levels of 0, 50, 100, 250 or 500 mg/kg/day. Females were dosed once daily, by oral gavage, from day 18 of pregnancy (rather than day 7 when implantation occurs as recommended in the guidance) and throughout lactation until day 20 post-partum, inclusive. The F1 offspring were not mated to assess reproductive performance. The daily oral administration of doxycycline hyclate elicited maternal toxicity at 500 mg/kg/day, which included noisy breathing, a reduction in bodyweight gain, a reduction in food consumption and an increased duration of gestation. There was also evidence of slight toxicity in the F1 generation, which was characterized by a reduction in bodyweight during lactation and post-weaning, generalized pallor and an increase in the numbers of litters containing one or more pups with clinical signs including hair-loss, piloerection and abnormal hair growth. At 250 mg/kg/day, there was evidence of slight maternal toxicity (e.g., reduction in bodyweight gain and food consumption, slight increase in the duration of gestation) and slight toxicity in the F1 generation (e.g., increase in the numbers of litters containing one or more pups with clinical signs including hair-loss, piloerection and abnormal hair growth). At 100mg/kg/day, there was an increase in the numbers of pups with hair-loss in the F1 generation but there was no apparent evidence of maternal toxicity at 100 or 50 mg/kg/day or toxicity in the F1 generation at 50 mg/kg/day.
REFERENCES
- 1. Del Rosso JQ, Webster G, Jackson M, Rendon M, Rich P, Torok H, MD, Bradshaw M. Two randomized phase III clinical trials evaluating anti-inflammatory dose doxycycline (40-mg doxycycline, USP capsules) administered once daily for treatment of rosacea. J Am Acad Dermatol. 2007;56(5):791-802.
- 2. Pruzanski W, Greenwald RA, Street IP, Laliberte F, Stefanski E, Vadas P. Inhibition of enzymatic activity of phospholipases A2 by minocycline and doxycycline. Biochem Pharmacol. 1992; 44(6):1165-70.
- 3. Product Monograph for Pr APPRILON® (doxycycline modified-release capsules) by Galderma Canada Inc. Control No.: 214275. Date of Revision: May 31, 2018.