


Product Monograph - SPC-Clarithromycin for Oral Suspension
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 10 / 2026 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS; General | 10 / 2026 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 5
1 INDICATIONS ...................................................................................................................... 5
1.1 Pediatrics ............................................................................................................................... 5
1.2 Geriatrics ............................................................................................................................... 5
2 CONTRAINDICATIONS ......................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ..................................................................... 7
4 DOSAGE AND ADMINISTRATION ......................................................................................... 7
4.1 Dosing Consideration ............................................................................................................ 7
4.2 Recommended Dose and Dosage Adjustment ..................................................................... 7
4.3 Reconstitution ....................................................................................................................... 8
4.4 Administration ....................................................................................................................... 9
4.5 Missed Dose .......................................................................................................................... 9
5 OVERDOSAGE ..................................................................................................................... 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .......................................... 9
7 WARNINGS AND PRECAUTIONS ........................................................................................ 10
7.1 Special Populations ............................................................................................................. 15
7.1.1 Pregnant Women ......................................................................................................... 15
7.1.2 Breast-feeding .............................................................................................................. 15
7.1.3 Pediatrics ..................................................................................................................... 15
7.1.4 Geriatrics ...................................................................................................................... 16
8 ADVERSE REACTIONS ........................................................................................................ 16
8.1 Adverse Reaction Overview ................................................................................................ 16
8.2 Clinical Trial Adverse Reactions .......................................................................................... 16
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .............................................................. 21
8.3 Less Common Clinical Trial Adverse Reactions ................................................................... 23
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ...................................... 23
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data…………………………………………………………………………………………………………………………………… 23
8.5 Post-Market Adverse Reactions ......................................................................................... 25
9 DRUG INTERACTIONS ....................................................................................................... 27
9.1 Serious Drug Interactions ................................................................................................... 27
9.2 Drug Interactions Overview................................................................................................ 27
9.3 Drug-Behavioural Interactions ........................................................................................... 28
9.4 Drug-Drug Interactions ....................................................................................................... 28
9.5 Drug-Food Interactions ....................................................................................................... 38
9.6 Drug-Herb Interactions........................................................................................................ 38
9.7 Drug-Laboratory Test Interactions ...................................................................................... 38
10 CLINICAL PHARMACOLOGY ............................................................................................. 38
10.1 Mechanism of Action ......................................................................................................... 38
10.3 Pharmacokinetics ............................................................................................................... 38
11 STORAGE, STABILITY AND DISPOSAL ............................................................................... 44
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................. 45
PART II: SCIENTIFIC INFORMATION ...................................................................................... 46
13 PHARMACEUTICAL INFORMATION .................................................................................. 46
14 CLINICAL TRIALS .............................................................................................................. 47
14.1 Trial Design and Study Demographics .............................................................................. 47
14.2 Study Results .................................................................................................................... 47
14.3 Comparative Bioavailability Studies ................................................................................. 49
15 MICROBIOLOGY .............................................................................................................. 54
16 NON-CLINICAL TOXICOLOGY ........................................................................................... 61
17 SUPPORTING PRODUCT MONOGRAPHS .......................................................................... 71
PATIENT MEDICATION INFORMATION ................................................................................. 72
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
SPC-Clarithromycin for Oral Suspension (clarithromycin for oral suspension) is indicated for the treatment of infections due to susceptible organisms, in the following conditions:
Upper Respiratory Tract
- Pharyngitis caused by S. pyogenes (Group A ß-hemolytic streptococci).
- Acute otitis media caused by H. influenzae, M. catarrhalis, or S. pneumoniae. See 14 CLINICAL TRIALS, Otitis Media.
Lower Respiratory Tract
- Mild to moderate community-acquired pneumonia caused by S. pneumoniae, C. pneumoniae, or M. pneumoniae. See 7 WARNINGS AND PRECAUTIONS, Sensitivity /Resistance.
Uncomplicated skin and skin structure infections
- Uncomplicated skin and skin structure infections (i.e., impetigo and cellulitis) caused by S. aureus or S. pyogenes. See 7 WARNINGS AND PRECAUTIONS, Sensitivity /Resistance.
Mycobacterial Infections
- Disseminated mycobacterial infections due to M. avium and M. intracellulare.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of SPC-Clarithromycin for Oral Suspension should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1 Pediatrics
Pediatrics (6 months - 12 years of age): Dosing recommendations for children are based on body weight. See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics and 4 DOSAGE AND ADMINISTRATION, Table 1.
1.2 Geriatrics
Geriatrics (> 65 years of age): Dosage adjustment should be considered in elderly patients with severe renal impairment. See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
SPC-Clarithromycin for Oral Suspension is contraindicated in:
- Patients with a known hypersensitivity to clarithromycin, erythromycin, other macrolide antibacterial agents or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. See 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with a history of cholestatic jaundice / hepatic dysfunction associated with prior use of clarithromycin.
- Patients who suffer from severe hepatic failure in combination with renal impairment. See 7 WARNINGS AND PRECAUTIONS, Hepatic /Biliary / Pancreatic, 7 WARNINGS AND PRECAUTIONS, Renal, 4 DOSAGE AND ADMINISTRATION, Dosing Considerations and 4 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment.
- Patients with history of QT prolongation (congenital or documented acquired QT prolongation) or ventricular cardiac arrhythmia, including torsades de pointes. See 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS, Drug-Drug Interactions.
- Patients with electrolyte disturbances (hypokalaemia or hypomagnesaemia, due to the risk of prolongation of the QT interval and torsades de pointes).
Concomitant therapy with astemizole, cisapride, domperidone, pimozide, terfenadine.
There have been post-marketing reports of drug interactions when clarithromycin and / or erythromycin are co-administered with astemizole, cisapride, pimozide, or terfenadine resulting in cardiac arrhythmias (QT prolongation, ventricular tachycardia, ventricular fibrillation, and torsades de pointes) most likely due to inhibition of hepatic metabolism of these drugs by erythromycin and clarithromycin. Fatalities have been reported. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12 .
- Concomitant therapy with saquinavir due to potentially life-threatening cardiac arrhythmia.
- Concomitant therapy with HMG-CoA reductase inhibitors (statins) that are extensively metabolized by CYP3A4 (lovastatin or simvastatin), due to an increased risk of myopathy, including rhabdomyolysis. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
- Concomitant therapy with ergot alkaloids (e.g., ergotamine or dihydroergotamine) as this may result in ergot toxicity. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
- Concomitant administration with oral midazolam. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
- Concomitant administration with lomitapide. See 9 DRUG INTERACTIONS.
- Concomitant therapy with colchicine due to the risk of life threatening and fatal colchicine toxicity. This risk may be further increased with concomitant medications metabolized by P-glycoprotein or strong CYP3A inhibitors. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
- Concomitant therapy with ivabradine due to potential increase in ivabradine levels and risk of excessive bradycardia. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12 .
- Concomitant therapy with ticagrelor or ranolazine*.
* Not marketed in Canada.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Consideration
- In patients with a combination of hepatic (mild to moderate) and renal impairments or in the presence of severe renal impairment, decreased dosage of clarithromycin or prolonged dosing intervals might be appropriate. See 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
- Clarithromycin is contraindicated in patients with severe hepatic failure in combination with renal impairment. See 2 CONTRAINDICATIONS.
- In children with renal impairment and a creatinine clearance < 30 mL/min, the dosage of SPC-Clarithromycin for Oral Suspension should be reduced by one-half, i.e., up to 250 mg once daily, or 250 mg twice daily in more severe infections. Dosage should not be continued beyond 14 days in these patients.
4.2 Recommended Dose and Dosage Adjustment
- The recommended daily dosage of SPC-Clarithromycin for Oral Suspension is 15 mg / kg / day, in divided doses every 12 hours, not to exceed 1000 mg/day. The usual duration of treatment is for 5 to 10 days depending on the pathogen involved and the severity of the condition. Treatment for pharyngitis caused by Streptococcal species should be 10 days.
- In children with renal impairment and a creatinine clearance < 30 mL / min, the dosage of SPC-Clarithromycin for Oral Suspension should be reduced by one-half, i.e., up to 250 mg once daily, or 250 mg twice daily in more severe infections. Dosage should not be continued beyond 14 days in these patients.
- Table 1 is a suggested guide for determining dosage.
Table1– SPC-Clarithromycin for Oral Suspension Pediatric Dosage Guidelines Based on Body Weight in kg
| 125 mg / 5 mL | 250 mg / 5 mL | ||||||
|---|---|---|---|---|---|---|---|
| Weight* | Dosage (mL) given twice daily | Dosage (mL) given twice daily | |||||
| 8 to 11 kg (1 to 2 years)** | 2.5 | 1.25 | |||||
| 12 to 19 kg (2 to 4 years) | 5 | 2.5 | |||||
| 20 to 29 kg (4 to 8 years) | 7.5 | 3.75 | |||||
| 30 to 40 kg (8 to 12 years) | 10 | 5 | |||||
* Children < 8 kg should be dosed on a per kg basis (approximately 7.5 mg / kg twice daily). ** Approximate ages. | |||||||
Children with Mycobacterial Infections
- Clarithromycin is recommended as the primary agent for the treatment of disseminated infection due to MAC. Clarithromycin should be used in combination with other antimycobacterial drugs which have shown in vitro activity against MAC, including ethambutol and rifampin. Although no controlled clinical trial information is available for combination therapy with clarithromycin, the U.S. Public Health Service Task Force has provided recommendations for the treatment of MAC.
- In children, the recommended dose is 7.5 mg / kg twice daily up to 500 mg twice daily clarithromycin per day in 2 divided doses. Dosing recommendations for children are shown in Table 1 above.
- Treatment of disseminated MAC infections in AIDS patients should continue for life if clinical and mycobacterial improvement are observed.
4.3 Reconstitution
Oral Solutions:
Directions for Reconstitution: 125 mg / 5 mL
- 55 mL size: Measure the required volume (35 mL) of water using a graduated cylinder. Add half the volume of water to the bottle and shake vigorously. Add the remainder of water to the bottle and shake. When reconstituted as directed, each teaspoonful (5 mL) contains: Clarithromycin 125 mg in a fruity-flavored, aqueous vehicle.
- 105 mL size: Measure the required volume (64 mL) of water using a graduated cylinder. Add half the volume of water to the bottle and shake vigorously. Add the remainder of water to the bottle and shake. When reconstituted as directed, each teaspoonful (5 mL) contains: Clarithromycin 125 mg in a fruity-flavored, aqueous vehicle.
- 150 mL size: Measure the required volume (91 mL) of water using a graduated cylinder. Add half the volume of water to the bottle and shake vigorously. Add the remainder of water to the bottle and shake. When reconstituted as directed, each teaspoonful (5 mL) contains: Clarithromycin 125 mg in a fruity-flavored, aqueous vehicle.
Directions for Reconstitution: 250 mg / 5 mL
105 mL size: Measure the required volume (64 mL) of water using a graduated
- cylinder. Add half the volume of water to the bottle and shake vigorously. Add the remainder of water to the bottle and shake. When reconstituted as directed, each teaspoonful (5 mL) contains: Clarithromycin 250 mg in a fruity-flavored, aqueous vehicle.
Shake until all the particles are suspended. Avoid vigorous and/or lengthy shaking. Shake prior to each subsequent use to ensure resuspension. After reconstitution, store between (15° C and 25° C) and use within 14 days. Do not refrigerate. Any reconstituted unused medication should be discarded after 14 days. The graduated syringe used for dosage administration should be rinsed between uses. Do not leave syringe in bottle. Do not store reconstituted suspension in syringe. See 11 STORAGE, STABILITY AND DISPOSAL.
4.4 Administration
SPC-Clarithromycin for Oral Suspension may be taken with or without food.
SPC-Clarithromycin for Oral Suspension sometimes has a bitter after taste, therefore, the suspension can be taken with food and / or juice.
4.5 Missed Dose
If a dose of clarithromycin is missed, the patient should take the dose as soon as possible and then return to their normal scheduled dose. However, if a dose is skipped, the patient should not double the next dose.
5 OVERDOSAGE
Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
Reports indicate that the ingestion of large amounts of clarithromycin can be expected to produce gastrointestinal symptoms. Adverse reactions accompanying overdosage should be treated by the prompt elimination of unabsorbed drug and supportive measures.
Clarithromycin is protein bound (70%). No data are available on the elimination of clarithromycin by hemodialysis or peritoneal dialysis.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composit ion | Non-medicinal Ingredients |
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
| oral | oral suspension / 125 mg / 5 mL and 250 mg / 5 mL | acetone, alginic acid, aspartame, castor oil, citric acid (anhydrous), colloidal silicon dioxide, croscarmellose sodium, flavour peppermint, flavour tutti frutti, hydroxypropyl cellulose, hypromellose, hypromellose phthalate, maltodextrin, povidone, sodium benzoate, sodium chloride, sodium citrate (dihydrate), sucrose, titanium dioxide and xanthan gum. |
SPC-Clarithromycin for Oral Suspension 125 mg / 5 mL is supplied as a granular preparation in 55 mL, 105 mL and 150 mL HDPE bottles.
SPC-Clarithromycin for Oral Suspension 250 mg / 5 mL is supplied as a granular preparation in 105 mL HDPE bottles.
SPC-Clarithromycin for Oral Suspension is supplied as a white to off-white granular powder, forming white to off-white suspension on constitution with water. The bottles allow capacity for shaking. When reconstituted, the concentration of clarithromycin is 125 mg/5 mL and 250 mg/5 mL respectively. The resulting suspension has a sweet taste and fruity flavor (tutti-fruity and peppermint).
SPC-Clarithromycin for Oral Suspension 125 mg / 5 mL and 250 mg / 5 mL oral suspensions contain less than 550 mg/mL of sucrose.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Clarithromycin should be administered with caution to any patient who has demonstrated some form of drug allergy, particularly to structurally related-drugs. If an allergic reaction to clarithromycin occurs, administration of the drug should be discontinued. Serious hypersensitivity reactions may require epinephrine, antihistamines, or corticosteroids. See 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity Reactions.
Long-term use may, as with other antibiotics, result in colonization with increased numbers of non-susceptible bacteria and fungi. If superinfections occur, appropriate therapy should be instituted.
Patients Infected with Human Immunodeficiency Virus
Several studies of Human Immunodeficiency Virus (HIV)-positive patients receiving clarithromycin for treatment of MAC infection have shown poorer survival in those patients randomized to receive doses higher than 500 mg twice daily. The explanation for the poorer survival associated with doses higher than 500 mg twice daily has not been determined.
Treatment or prophylaxis of MAC infection with clarithromycin should not exceed the approved dose of 500 mg twice daily.
Myasthenia Gravis
Exacerbation of symptoms of myasthenia gravis and new onset of symptoms of myasthenic syndrome has been reported in patients receiving clarithromycin therapy.
Atypical Antipsychotics (quetiapine)
Due to inhibition of CYP3A by clarithromycin, co-administration of clarithromycin with quetiapine results in increased quetiapine concentrations. Serious and life-threatening quetiapine-related adverse reactions, including malignant neuroleptic syndrome, have been reported. Clarithromycin should not be used in combination with quetiapine unless clinically necessary. See 9 DRUG INTERACTIONS. Monitoring and dose reductions may be required.
Oral Hypoglycemic Agents / Insulin
The concomitant use of clarithromycin and oral hypoglycaemic agents (such as sulphonylurias) and / or insulin can result in significant hypoglycaemia. Careful monitoring of glucose is recommended. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
Oral Anticoagulants
There is a risk of serious hemorrhage and significant elevations in International Normalized Ratio (INR) and prothrombin time when clarithromycin is co-administered with warfarin. INR and prothrombin times should be frequently monitored while patients are receiving clarithromycin and oral anticoagulants concurrently. See 9 DRUG INTERACTIONS, 9.4 Drug- Drug Interactions, Table 12.
Caution should be exercised when clarithromycin is co-administered with direct acting oral anticoagulants such as dabigatran, rivaroxaban, apixaban and edoxaban, particularly to patients at high risk of bleeding. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions.
HMG-CoA Reductase Inhibitors
Concomitant use of clarithromycin with lovastatin or simvastatin is contraindicated. See 2 CONTRAINDICATIONS. Caution should be exercised when prescribing clarithromycin with other statins. Rhabdomyolysis has been reported in patients taking clarithromycin and statins. Patients should be monitored for signs and symptoms of myopathy. In situations where the concomitant use of clarithromycin with statins cannot be avoided, it is recommended to prescribe the lowest registered dose of the statin. Use of a statin that is not dependent on CYP3A metabolism (e.g., fluvastatin) can be considered. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
Triazolobenzodiazepines and Related Benzodiazepines
Caution is advised regarding the concomitant administration of clarithromycin with triazolobenzodiazepines (such as triazolam and alprazolam), or with other benzodiazepines (such as intravenous midazolam) due to the serious risk of central nervous system (CNS) effects (e.g., somnolence and confusion). See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
Concomitant administration with oral midazolam is contraindicated. See 2 CONTRAINDICATIONS.
Calcium Channel Blockers
Caution is advised regarding the concomitant administration of clarithromycin and calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem) due to the risk of hypotension. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
Hypotension, bradyarrhythmias, and lactic acidosis have been observed in patients receiving concurrent verapamil, belonging to the calcium channel blockers drug class. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Table 12.
Other Drugs
Use of clarithromycin with other drugs may lead to drug-drug interaction, see 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY
Cardiovascular
Cardiovascular Events
Prolonged cardiac repolarisation and QT interval, imparting a risk of developing cardiac arrhythmia and torsades de pointes, have been seen in treatment with macrolides, including clarithromycin. See 8 ADVERSE REACTIONS. Fatalities have been reported. Elderly patients may be more susceptible to drug-associated effects on the QT interval.
As the following situations may lead to an increased risk for ventricular arrhythmias (including torsades de pointes), clarithromycin should be used with caution in patients with coronary artery disease, cardiac insufficiency, conduction disturbances, clinically significant bradycardia (e.g., < 50 bpm), or when concomitantly taking with other medicinal products associated with QT prolongation, due to the risk for QT prolongation and torsades de pointes. See 9 DRUG INTERACTIONS. Clarithromycin must not be given to patients with electrolyte disturbances such as hypomagnesaemia or hypokalemia. See 2 CONTRAINDICATIONS.
Clarithromycin is contraindicated in patients with congenital or documented acquired QT prolongation or history of ventricular arrhythmia, including torsades de pointes. Clarithromycin is also contraindicated in patients with hypokalaemia due to the risk of QT prolongation and torsades de pointes. Concomitant administration of clarithromycin with astemizole, cisapride, domperidone, pimozide, terfenadine and saquinavir is also contraindicated. See 2 CONTRAINDICATIONS.
Epidemiological studies investigating the risk of adverse cardiovascular outcomes with macrolides have shown variable results. Studies have identified risks of arrhythmia, myocardial infarction and cardiovascular mortality associated with macrolides including clarithromycin. Consideration of these findings should be balanced with treatment benefits when prescribing clarithromycin.
Driving and Operating Machinery
There are no data on the effect of clarithromycin on the ability to drive or use machines. The potential for dizziness, vertigo, confusion and disorientation, which may occur with the medication, should be taken into account before patients drive or use machines.
Endocrine and Metabolism
SPC-Clarithromycin for Oral Suspension contains sucrose. Patients with rare hereditary problems of fructose intolerance, glucose-galactose malabsorption or sucrase-isomaltase insufficiency should not take this medicine.
When prescribing to diabetic patients, the sucrose content should be taken into account. See 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Phenylketonuric Patients
SPC-Clarithromycin for Oral Suspension contains aspartame. Aspartame contains phenylalanine which may pose safety risks in phenylketonuric (PKU) patients. See 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Gastrointestinal
Clostridioides difficile-Associated Disease
Clostridioides difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including clarithromycin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridioides difficile. Clostridioides difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridioides difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial drug clinically effective against Clostridioides difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases. See 8 ADVERSE REACTIONS.
Hepatic / Biliary / Pancreatic
Caution is advised in patients with impaired hepatic function.
Clarithromycin is principally excreted by the liver and kidney. In patients with a combination of hepatic (mild to moderate) and renal impairments, decreased dosage of clarithromycin or prolonged dosing intervals might be appropriate. See 4 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment.
Clarithromycin is contraindicated in patients with severe hepatic failure in combination with renal impairment. See 2 CONTRAINDICATIONS.
Hepatic dysfunction, including increased liver enzymes, and hepatocellular and / or cholestatic hepatitis, with or without jaundice, has been reported with clarithromycin. This hepatic dysfunction may be severe and is usually reversible. In some instances, hepatic failure with fatal outcomes has been reported and generally has been associated with serious underlying diseases and / or concomitant medications. Discontinue clarithromycin immediately if signs and symptoms of hepatitis occur, such as anorexia, jaundice, dark urine, pruritus, or tender abdomen.
Immune
Hypersensitivity Reactions
In the event of severe acute hypersensitivity reactions, such as anaphylaxis, severe cutaneous adverse reactions (SCAR) (e.g., acute generalized exanthematous pustulosis (AGEP), Stevens- Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and drug rash with eosinophilia and systemic symptoms (DRESS)), clarithromycin therapy should be discontinued immediately and appropriate treatment should be urgently initiated.
Renal
Caution should be exercised when administering clarithromycin to patients with moderate to severe renal impairment.
Clarithromycin is principally excreted by the liver and kidney. In patients with a combination of hepatic (mild to moderate) and renal impairments or in the presence of severe renal impairment, decreased dosage of clarithromycin or prolonged dosing intervals might be appropriate. See 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
Clarithromycin is contraindicated in patients with severe hepatic failure in combination with renal impairment. See 2 CONTRAINDICATIONS.
Reproductive Health: Female and Male Potential
Fertility
See 16 NON-CLINICAL TOXICOLOGY; Reproductive and Developmental Toxicology. Please See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX. See 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women.
Teratogenic Risk
Please See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX. See 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women.
Sensitivity / Resistance
The development of resistance (11 out of 19 breakthrough isolates in 1 study) has been seen in HIV positive patients receiving clarithromycin for prophylaxis and treatment of MAC infection.
In view of the emerging resistance of Streptococcus pneumoniae, Staphylococcus aureus and Streptococcus pyogenes to macrolides, it is important that susceptibility testing be performed when prescribing clarithromycin for community-acquired pneumonia and uncomplicated skin and skin structure infections.
To avoid failure of the eradication treatment with a potential for developing antimicrobial resistance and a risk of failure with subsequent therapy, patients should be instructed to follow closely the prescribed regimen.
Development of Drug-Resistant Bacteria
Prescribing SPC-Clarithromycin for Oral Suspension in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
7.1 Special Populations
7.1.1 Pregnant Women
Clarithromycin should not be used in pregnancy except where no alternative therapy is appropriate, particularly during the first 3 months of pregnancy. If pregnancy occurs while taking the drug, the patient should be apprised of the potential hazard to the fetus. See 3 Serious Warnings and Precautions Box.
There are no adequate and well-controlled studies in pregnant women. The benefits against risk, particularly during the first 3 months of pregnancy should be carefully weighed by a physician. Based on variable results obtained from animal studies and experience in humans, the possibility of adverse effects on embryofoetal development cannot be excluded. Some observational studies evaluating exposure to clarithromycin during the first and second trimester have reported an increased risk of miscarriage compared to no antibiotic use or other antibiotic use during the same period. The available epidemiological studies on the risk of major congenital malformations with use of macrolides including clarithromycin during pregnancy provide conflicting results. Therefore, use during pregnancy is not advised without carefully weighing the benefits against risks.
Four teratogenicity studies in rats (3 with oral doses and 1 with intravenous doses up to 160 mg / kg / day administered during the period of major organogenesis) and 2 in rabbits (at oral doses up to 125 mg / kg / day or intravenous doses of 30 mg/kg/day administered during gestation days 6 to 18) failed to demonstrate any teratogenicity from clarithromycin. Two additional oral studies in a different rat strain at similar doses and similar conditions demonstrated a low incidence of cardiovascular anomalies at doses of 150 mg /kg / day administered during gestation days 6 to 15. Plasma levels after 150 mg / kg/ day were 2 times the human serum levels.
Four studies in mice revealed a variable incidence of cleft palate following oral doses of 1000 mg /kg / day during gestation days 6 to 15. Cleft palate was also seen at 500 mg / kg/ day. The 1000 mg /kg / day exposure resulted in plasma levels 17 times the human serum levels. In monkeys, an oral dose of 70 mg /kg / day produced fetal growth retardation at plasma levels that were 2 times the human serum levels.
Embryonic loss has been seen in monkeys and rabbits. See 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology.
7.1.2 Breast-feeding
The safety of clarithromycin for use during breast-feeding of infants has not been established. Clarithromycin is excreted in human breast milk in small amounts. It has been estimated that an exclusively breastfed infant would receive about 1.7% of the maternal weight-adjusted dose of clarithromycin.
Preweaned rats, exposed indirectly via consumption of milk from dams treated with 150 mg /kg / day for 3 weeks, were not adversely affected, despite data indicating higher drug levels in milk than in plasma.
7.1.3 Pediatrics
Pediatrics (6 months to 12 years of age):
Use of clarithromycin for oral suspension in children under 6 months has not been studied. In pneumonia, clarithromycin granules were not studied in children younger than 3 years.
The safety of clarithromycin has not been studied in MAC patients under the age of 20 months.
Neonatal and juvenile animals tolerated clarithromycin in a manner similar to adult animals. Young animals were slightly more intolerant to acute overdosage and to subtle reductions in erythrocytes, platelets and leukocytes, but were less sensitive to toxicity in the liver, kidney, thymus and genitalia.
Increased valproate and phenobarbital concentrations and extreme sedation were noted in a 3-year old patient coincident with clarithromycin therapy. Cause and effect relationship cannot be established. However, monitoring of valproate and phenobarbital concentrations may be considered.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Dosage adjustment should be considered in elderly patients with severe renal impairment. In a steady-state study in which healthy elderly subjects (age 65 to 81 years old) were given 500 mg every 12 hours, the maximum concentrations of clarithromycin and 14-OH-clarithromycin were increased. The AUC was also increased. These changes in pharmacokinetics parallel known age-related decreases in renal function. In clinical trials, elderly patients did not have an increased incidence of adverse events when compared to younger patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The majority of side effects observed in clinical trials involving 3563 patients treated with clarithromycin tablets were of a mild and transient nature. Fewer than 3% of adult patients without mycobacterial infections discontinued therapy because of drug-related side-effects. The most common drug-related adverse reactions in adults taking clarithromycin tablets were nausea, diarrhea, abdominal pain, dyspepsia, headache, dysgeusia (taste perversion) and vomiting. In pediatric patients taking clarithromycin for oral suspension, the most frequently reported events were diarrhea, vomiting, abdominal pain, dyspepsia, taste perversion and infection.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Clarithromycin tablets
Patients with Respiratory Tract or Skin Infections
Table 2 provides a listing of adverse reactions from clinical trials or post-marketing surveillance as well as adverse events reported during post-marketing surveillance. Adverse events reported during post-marketing surveillance may include patients treated for various infections and are not limited to patients with respiratory tract or skin infections.
| Table 2 Adverse Events/Adverse Drug Reactions in Patients with Respiratory Tract or Skin Infections or Other Infections Treated with Clarithromycin Tablets | ||
| Table 2 Adverse Events/Adverse Drug Reactions in Patients with Respiratory Tract or Skin Infections or Other Infections Treated with Clarithromycin Tablets | ||
| Table 2 Adverse Events/Adverse Drug Reactions in Patients with Respiratory Tract or Skin Infections or Other Infections Treated with Clarithromycin Tablets | ||
| System Organ Class | Adverse Reaction/Adverse Event | |
| System Organ Class | Adverse Reaction/Adverse Event | |
| System Organ Class | Adverse Reaction/Adverse Event | |
| Blood and lymphatic system disorders | Eosinophilia Anemia Leukopenia Thrombocythemia Thrombocytopenia | |
| Cardiac disorders* | Electrocardiogram QT prolonged Ventricular tachycardia Torsades de pointes | |
| Ear and labyrinth disorders | Vertigo Tinnitus Ear disorder Deafness**** | |
| Eye disorders | Visual disturbance Conjunctivitis | |
| Gastrointestinal disorders | Constipation Flatulence Dry mouth Glossitis Stomatitis Gastrointestinal disorder Tongue discolouration Tooth discolouration Pancreatitis | |
| General disorders and administration site conditions | Asthenia Pain Chest pain | |
| Hepatobiliary disorders | Hepatomegaly Hepatic function abnormal Hepatitis Hepatitis cholestatic Jaundice (cholestatic and hepatocellular) Hepatic failure *** | |
| Immune system disorders | Anaphylactic reaction Myasthenia gravis | |
| Infections and infestations | Infection Colitis pseudomembranous Candidiasis Rhinitis Pharyngitis Vaginal candidiasis Vaginal infection | |
| Investigations | Increased liver enzymes | |
| Metabolism and nutrition disorders | Anorexia Hypoglycemia** | |
| Musculoskeletal and connective tissue disorders | Back pain Myalgia | |
| Nervous system disorders | Dizziness Somnolence Convulsion Parosmia Dysgeusia Ageusia | |
| Psychiatric disorders | Nervousness Anxiety Insomnia Nightmare Depression Confusional state Disorientation Depersonalisation Hallucination Psychotic disorder | |
| Renal and urinary disorders | Hematuria Nephritis interstitial | |
| Reproductive system and breast disorders | Dysmenorrhea | |
| Respiratory, thoracic and mediastinal disorders | Cough Dyspnea Asthma | |
| Skin and subcutaneous tissue disorders | Severe cutaneous adverse reactions (SCAR) (e.g., Acute generalized exanthematous pustulosis (AGEP) Stevens-Johnson syndrome (SJS) Toxic epidermal necrosis (TEN) Drug rash with eosinophilia and systemic symptoms (DRESS)) Pruritus Rash Hyperhidrosis Urticaria | |
* As with other macrolides, QT prolongation, ventricular tachycardia, and torsades de pointes have been reported with clarithromycin. ** There have been reports of hypoglycemia, some of which have occurred in patients on concomitant oral hypoglycemic agents or insulin. *** Hepatic dysfunction may be severe and is usually reversible. Hepatic failure with fatal outcome has been reported and generally has been associated with serious underlying diseases and/or concomitant medications. **** There have been reports of hearing loss with clarithromycin which is usually reversible upon withdrawal of therapy. | ||
In studies of adults with pneumonia comparing clarithromycin to erythromycin base or erythromycin stearate, there were significantly fewer adverse events involving the digestive system in patients treated with clarithromycin.
Patients with Mycobacterial Infections
In patients with acquired immune deficiency syndrome (AIDS) and other immunocompromised patients treated with the higher doses of clarithromycin over long periods of time for prevention or treatment of mycobacterial infections, it was often difficult to distinguish adverse events possibly associated with clarithromycin administration from underlying signs of HIV disease or intercurrent illness.
Prophylaxis
Discontinuation due to adverse events was required in 18% of AIDS patients receiving clarithromycin 500 mg twice daily, compared to 17% of patients receiving placebo in a randomized, double-blind study. Primary reasons for discontinuation in the clarithromycin-treated patients include headache, nausea, vomiting, depression and taste perversion. The most frequently reported adverse events with an incidence of 2% or greater, excluding those due to the patient's concurrent condition, are listed in Table 3. Among these events, taste perversion was the only event that had significantly higher incidence in the clarithromycin-treated compared to the placebo-treated group.
| Table 3 Percentage of Adverse Events* in Immunocompromised Adult Patients Receiving Prophylaxis Against M. avium Complex | |||||||
|---|---|---|---|---|---|---|---|
| System Organ Class‡ | Adverse Reaction | Clarithromycin (n=339) % | Placebo (n = 339) % | ||||
| Gastrointestinal disorders | Abdominal pain | 5.0% | 3.5% | ||||
| Nausea | 11.2% | 7.1% | |||||
| Diarrhea | 7.7% | 4.1% | |||||
| Vomiting | 5.9% | 3.2% | |||||
| Dyspepsia | 3.8% | 2.7% | |||||
| Flatulence | 2.4% | 0.9% | |||||
| Nervous system disorders | Dysgeusia | 8.0% | 0.3% | ||||
| Headache | 2.7% | 0.9% | |||||
| Skin and subcutaneous tissue disorders | Rash | 3.2% | 3.5% | ||||
* Includes those events possibly or probably related to study drug and excludes concurrent conditions. ‡ ≥ 2% Adverse Event Incidence Rates for either treatment group. | |||||||
Treatment of Patients with Mycobacterial Infections
Excluding those patients who discontinued therapy due to complications of their underlying non-mycobacterial diseases (including death), approximately 14% of the patients discontinued therapy due to drug-related adverse events.
In adult patients, the most frequently reported adverse events with an incidence of 3% or greater, excluding those due to the patient's concurrent condition, are listed in Table 4 by the total daily dose the patient was receiving at the time of the event. A total of 867 patients were treated with clarithromycin for mycobacterial infections. Of these, 43% reported one or more adverse events. Most of these events were described as mild to moderate in severity, although 14% were described as severe.
Incidence of adverse events was higher in patients taking 4000 mg total daily doses compared to lower doses (Table 4).
| Table 4 Percentage of Adverse Events* in Immunocompromised Adult Patients Treated with Clarithromycin for Mycobacterial Infections Presented by Total Daily Dose at Time of the Event | |||||||||
| System Organ Class | Adverse Reaction | 1000 mg (n=463) | 2000 mg (n=516) | 4000 mg (n=87) | |||||
| Ear and labyrinth disorders | Hearing impaired** | 3% | 2% | 5% | |||||
| Gastrointestinal disorders | Nausea | 11% | 16% | 40% | |||||
| Vomiting | 7% | 9% | 24% | ||||||
| Abdominal Pain | 5% | 7% | 20% | ||||||
| Diarrhea | 4% | 6% | 17% | ||||||
| Flatulence | 1% | 2% | 7% | ||||||
| Constipation | 1% | < 1% | 5% | ||||||
| Dry Mouth | < 1% | 0% | 5% | ||||||
| Investigations | Aspartate aminotransferase increased | 2% | 2% | 11% | |||||
Alanine aminotransferase increased | 1% | 1% | 9% | ||||||
| Nervous system disorders | Dysgeusia | 6% | 7% | 29% | |||||
| Headache | 2% | 2% | 7% | ||||||
| Psychiatric disorders | Insomnia | < 1% | < 1% | 6% | |||||
Respiratory, thoracic and mediastinal disorders | Dyspnea | < 1% | < 1% | 7% | |||||
Skin and subcutaneous tissue disorders | Rash | 4% | 3% | 2% | |||||
* Related adverse events considered to be definitely, probably, possibly or remotely related to study events. ** Sum of patients with deafness, ear disorder, partial transitory deafness, and/or tinnitus. n = Number of adverse events. | |||||||||
A limited number of pediatric AIDS patients have been treated with clarithromycin suspension for mycobacterial infections. The most frequently reported adverse events, excluding those due to the patient's concurrent condition, are listed in Table 5 by the total daily dose of clarithromycin the patient received.
| Table 5 Number of Pediatric AIDS Patients Treated with Clarithromycin for Mycobacterial Infections Who Experienced Adverse Events Presented by Total Daily Dose at Time of the Event | |||||||
|---|---|---|---|---|---|---|---|
| System Organ Class | Adverse Event | < 15 mg/kg/day (n=19) | 15 to < 25 mg/kg/day (n=13) | ≥ 25 mg/kg/day (n=12) | |||
| Ear and labyrinth disorders | Tinnitus | 2 | 0 | 0 | |||
| Deafness | 1 | 1 | 0 | ||||
| Gastrointestinal disorders | Vomiting | 1 | 0 | 0 | |||
| Nausea | 1 | 0 | 0 | ||||
| Abdominal Pain | 1 | 0 | 0 | ||||
| Pancreatitis | 1 | 0 | 0 | ||||
| Investigations | Amylase Increased | 0 | 0 | 1 | |||
| Skin and subcutaneous tissue disorders | Purpuric Rash | 1 | 0 | 0 | |||
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Clarithromycin for Oral Suspension:
The safety profile of clarithromycin for oral suspension is similar to that of the 250 mg tablet in adult patients.
As with other macrolides, hepatic dysfunction, including increased liver enzymes, and hepatocellular and / or cholestatic hepatitis, with or without jaundice, has been infrequently reported with clarithromycin for oral suspension. This hepatic dysfunction may be severe and is usually reversible. In very rare instances, hepatic failure with fatal outcome has been reported and generally has been associated with serious underlying diseases and/or concomitant medications.
Allergic reactions ranging from urticaria and mild skin eruptions to anaphylaxis and Stevens-Johnson Syndrome / toxic epidermal necrolysis have occurred with orally administered clarithromycin.
There have been rare reports of pancreatitis and convulsions.
Of the 1829 patients who received clarithromycin for oral suspension, 571 (31%) reported at least one adverse event. The adverse events reported are summarized in Table 6.
| Table 6 Adverse Events Reported in Pediatric Clinical Trials | ||||
|---|---|---|---|---|
| Table 6 Adverse Events Reported in Pediatric Clinical Trials | ||||
| System Organ Class | Number (%) of Patients N=1829 | |||
| System Organ Class | Number (%) of Patients N=1829 | |||
| Blood and the lymphatic system disorders | 14 (< 1%) | |||
| Ear and labyrinth disorders | 25 (1%) | |||
| Eye disorders | 22 (1%) | |||
| Gastrointestinal disorders | 355 (19%) | |||
| General disorders and administration site conditions | 56 (3%) | |||
| Infections and infestations | 172 (9%) | |||
| Injury, poisoning and procedural complications | 19 (1%) | |||
| Investigations | 29 (2%) | |||
| Metabolism and nutrition disorders | 9 (< 1%) | |||
| Musculoskeletal and connective tissue disorders | 2 (< 1%) | |||
| Neoplasms benign, malignant and unspecified (including cysts and polyps) | 1 (< 1%) | |||
| Nervous system disorders | 41 (2%) | |||
| Psychiatric disorders | 12 (0.7%) | |||
| Renal and urinary disorders | 5 (< 1%) | |||
| Reproductive system and breast disorders | 2 (< 1%) | |||
| Respiratory, thoracic and mediastinal disorders | 61 (3%) | |||
| Skin and subcutaneous disorders | 66 (4%) | |||
| Vascular disorders | 2 (< 1%) | |||
| TOTAL* | 571 (31%) | |||
| * Patients with more than one event within a system organ class are only counted once in the total for that system organ class. Patients with events in more than one system organ class are counted only once in the overall total. | ||||
The majority of the patients reported adverse event in the Gastrointestinal disorders SOC (19%), and the Infections and infestations SOC (9%).
The events occurring most frequently in the Gastrointestinal disorder SOC were diarrhea (7%), vomiting (7%), abdominal pain (3%), dyspepsia (3%) and nausea (1%).
Other adverse events included infection (3%), rhinitis (2.2%), rash (2.2%), increased cough (2.1%), fever (2.2%), headache (1.6%), conjunctivitis (1.1%), dysgeusia (3%) and transient elevation of AST (0.9%).
The majority of adverse events were considered by the investigators to have either mild or moderate severity. Three hundred and seventy-five of 1829 patients (21%) had mild adverse events, 175 / 1829 patients (10%) had moderate adverse events and 20 /1 829 patients (1%) had severe adverse events.
In the 2 U.S. acute otitis media studies of clarithromycin versus antimicrobial / beta-lactamase inhibitor, the incidence of adverse events in all patients treated, primarily diarrhea (15% vs. 38%) and diaper rash (3% vs. 11%) in young children, was clinically or statistically lower in the clarithromycin arm versus the control arm.
In another U.S. otitis media study of clarithromycin versus cephalosporin, the incidence of adverse events in all patients treated, primarily diarrhea and vomiting, did not differ clinically or statistically for the 2 agents.
8.3 Less Common Clinical Trial Adverse Reactions
Clarithromycin Tablets:
The following adverse drug reactions are applicable to all indications approved for this formulation.
Blood and Lymphatic System Disorders:
eosinophilia and neutropenia
Gastrointestinal Disorders:
abdominal distension
General Disorders and Administration Site Conditions:
chest pain, chills, fatigue, influenza and malaise
Hepatobiliary Disorders:
cholestasis, gamma-glutamyltransferase increased and hepatitis
Investigations:
blood alkaline phosphatase increased and blood lactate dehydrogenase increased
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
Clarithromycin for Oral Suspension:
The following adverse drug reactions are applicable to all indications approved for this formulation.
Blood and Lymphatic System Disorders:
thrombocythemia
General Disorders and Administration Site Conditions:
pyrexia
Infections and Infestations:
infection
Musculoskeletal and Connective Tissue Disorders:
muscle spasms
Psychiatric Disorders:
nervousness
Skin and Subcutaneous Tissue Disorders:
rash maculo-papular
Other adverse reactions have been observed in different patient populations and during post-marketing surveillance. See 8 ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Table 2.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Clarithromycin Tablets:
Patients with Respiratory Tract or Skin Infections
Changes in laboratory values with possible clinical significance reported during clinical studies or during post-marketing surveillance are displayed in Table 7.
Table 7 - Abnormal Hematologic and Clinical Chemistry Findings in Patients with Respiratory Tract or Skin Infections Treated with Clarithromycin Tablets
System Organ Class | Laboratory Values | Frequency |
|---|---|---|
| Investigations | Alanine aminotransferase increased Aspartate aminotransferase increased Gamma-glutamyltransferase increased Blood alkaline phosphatase increased Blood lactate dehydrogenase increased Blood bilirubin increased Blood creatinine increased White blood cell count decreased | Uncommon (Less than 1%) |
Prothrombin time prolonged Blood urea increased | 1% 4% |
Patients with Mycobacterial Infections
In immunocompromised patients receiving prophylaxis against M. avium, those laboratory values outside the extreme high or low limit for the specified test were analyzed (Table 8).
Table 8 - Percentage of Patients* Exceeding Extreme Laboratory Value in Immunocompromised Patients Receiving Prophylaxis Against M. avium Complex
System Organ Class | Laboratory Values | Clarithromycin 500 mg b.i .d. | Placebo | ||||||
|---|---|---|---|---|---|---|---|---|---|
| Investigations | Hemoglobin decreased < 8 g/dL | 4/118 | 3% | 5/103 | 5% | ||||
Platelet count decreased < 50 x 109/L | 11/249 | 4% | 12/250 | 5% | |||||
White blood cell count decreased < 1 x 10⁹/L | 2/103 | 4% | 0/95 | 0% | |||||
Aspartate aminotransferase increased > 5 x ULN | 7/196 | 4% | 5/208 | 2% | |||||
Alanine aminotransferase increased > 5 x ULN | 6/217 | 3% | 4/232 | 2% | |||||
Blood alkaline phosphatase increased > 5 x ULN | 5/220 | 2% | 5/218 | 2% | |||||
* Includes only patients with ba seline values within the normal range or borderline high (hematology variables) and within the normal range or borderline low (chemistry variables). Legend: b.i.d. = twice daily; ULN = Upper Limit of Normal | |||||||||
Treatment of Patients with Mycobacterial Infections
In immunocompromised patients treated with clarithromycin for mycobacterial infections, evaluations of laboratory values were made by analysing those values outside the seriously abnormal level (i.e., the extreme high or low limit) for the specified test (Table 9 and Table 10).
Table 9 - Percentage of Immunocompromised Adult Patients Treated with Clarithromycin for Mycobacterial Infections who had On-Treatment Laboratory Values that Were Outside the Seriously Abnormal Level Presented by Total Daily Dose
System Organ Class | Laboratory Values | Seriously Abnormal Level | 1000 mg | 2000 mg | 4000 mg | |||||
|---|---|---|---|---|---|---|---|---|---|---|
| Investigations | Aspartate aminotransferase increased | > 5 x ULN | 3% | 2% | 4% | |||||
Alanine aminotransferase increased | > 5 x ULN | 2% | 2% | 7% | ||||||
| Platelet count decreased | < 50 x 109/L | 2% | 2% | 4% | ||||||
| White blood cell count decreased | < 1 x 10⁹/L | 0% | 2% | 0% | ||||||
| Blood urea increased | > 50 mg/dL | <1% | <1% | 4% | ||||||
| Legend: ULN = Upper Limit of Normal. | ||||||||||
Table 10 Number of Pediatric AIDS Patients Treated with Clarithromycin for Mycobacterial Infections who had On-Treatment Laboratory Values that Were Outside the Seriously Abnormal Level Presented by Total Daily Dose
System Organ Class | Laboratory Values | Seriously Abnormal Level | < 15 mg/kg/day | 15 to < 25 mg/kg/day | ≥ 25 mg/kg/day | |||||
|---|---|---|---|---|---|---|---|---|---|---|
| Investigations | Alanine aminotransferase increased | > 5 x ULN | 0 | 1 | 0 | |||||
Blood bilirubin increased | > 12 mg/dL | 1 | 0 | 0 | ||||||
| Platelet count decreased | < 50 x 109/L | 0 | 1 | 0 | ||||||
| Blood urea increased | > 50 mg/dL | 0 | 1 | 0 | ||||||
| Legend: ULN = Upper Limit of Normal. | ||||||||||
8.5 Post-Market Adverse Reactions
The following list of adverse events is a compilation of adverse reactions from Post-marketing Surveillance and Post-marketing Clinical Studies for all clarithromycin formulations.
| Table 11 Post-Market Adverse Drug Reactions | |||
| Table 11 Post-Market Adverse Drug Reactions | |||
| System Organ Class | Adverse Event | ||
| System Organ Class | Adverse Event | ||
| Blood and lymphatic system disorders | Agranulocytosis, leukopenia, thrombocytopenia | ||
| Cardiac disorders1 | Atrial fibrillation, cardiac arrest, electrocardiogram QT prolonged, extrasystoles, palpitations, Torsades de pointes, ventricular fibrillation, ventricular tachycardia | ||
| Ear and labyrinth disorders | Deafness, hearing impaired, hearing loss2, tinnitus, vertigo | ||
| Gastrointestinal disorders | Abdominal pain, constipation, dry mouth, dyspepsia, eructation, esophagitis, flatulence, gastritis, glossitis, pancreatitis, stomatitis, tongue discolouration, tooth discolouration, vomiting | ||
| General disorders and administration site conditions | Asthenia | ||
| Hepatobiliary disorders | Hepatic failure3, hepatitis, hepatitis cholestatic, jaundice (cholestatic and hepatocellular) | ||
| Immune system disorders | Angioedema, anaphylactic reaction, anaphylactoid reaction, anaphylaxis, hypersensitivity, myasthenia gravis | ||
| Infections and infestations | Candidiasis, cellulitis, pseudomembranous colitis, vaginal infection | ||
| Investigations | Albumin globulin ratio abnormal, alanine aminotransferase increased, aspartate aminotransferase increased, blood creatinine increased, blood urea increased, international normalized ratio (INR) increased4, liver enzymes increased, liver function test abnormal, prothrombin time prolonged4, urine color abnormal5 | ||
| Metabolism and nutrition disorders | Anorexia, decreased appetite | ||
| Musculoskeletal and connective tissue disorders | Musculoskeletal stiffness, myalgia, myopathy, rhabdomyolysis6 | ||
| Nervous system disorders | Ageusia, alteration of sense of smell, anosmia, convulsions, dizziness, dysgeusia, dyskinesia, headache, loss of consciousness, paraesthesia, parosmia, tremor, somnolence | ||
| Psychiatric disorders | Abnormal dreams, anxiety, confusion, depersonalization, depression, disorientation, hallucination, insomnia, mania, psychosis | ||
| Renal and urinary disorders | Interstitial nephritis, renal failure | ||
| Respiratory, thoracic and mediastinal disorders | Asthma, pulmonary embolism | ||
| Skin and subcutaneous tissue disorders | Severe cutaneous adverse reactions (SCAR) (e.g., acute generalized exanthematous pustulosis (AGEP), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug rash with eosinophilia and systemic symptoms (DRESS)), acne, dermatitis bullous, Henoch-Schonlein purpura, hyperhidrosis, pruritus, rash, urticaria | ||
| Vascular disorders | Hemorrhage4, vasodilation | ||
5 Symptom of hepatic failure.
| |||
Colchicine
There have been post-marketing reports of colchicine toxicity with concomitant use of clarithromycin and colchicine, especially in the elderly, some of which occurred in patients with renal insufficiency. Deaths have been reported in some patients. See 2 CONTRAINDICATIONS.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Many categories of drugs are metabolized by CYP3A and / or transported by P-gp located in the liver and in the intestine. Some drugs may inhibit or induce the activities of CYP3A and / or P-gp. Administration of such inhibitors or inducers may impact upon the metabolism. In some cases serum concentrations may be increased and in others decreased. Care must therefore be exercised when co-administering such drugs.
Effects of Clarithromycin on Other Drugs
Clarithromycin is an inhibitor of CYP3A and P-gp. This inhibition may lead to increased or prolonged serum levels of those drugs also metabolized by CYP3A or transported by P-gp when co-administered with clarithromycin. For such drugs the monitoring of their serum concentrations may be necessary.
Clarithromycin should be used with caution in patients receiving treatment with other drugs known to be CYP3A and / or P-gp substrates, especially if the CYP3A / P-gp substrate has a narrow safety margin (e.g., carbamazepine) and / or the substrate is extensively metabolized by CYP3A or transported by P-gp. Dosage adjustments may be considered, and when possible, serum concentrations of these drugs should be monitored closely in patients concurrently receiving clarithromycin.
Clarithromycin should be used with caution in patients receiving treatment with hydroxychloroquine and chloroquine as these medicines are known to prolong the QT interval due to the potential to induce cardiac arrhythmia and serious adverse cardiovascular events.
The following drugs or drug classes are known or suspected to be metabolized by the same CYP3A isozyme: alprazolam, astemizole, carbamazepine, cilostazol, cisapride, corticosteroids (e.g. Methylprednisolone), cyclosporine, disopyramide, domperidone, ergot alkaloids, ibrutinib, ivabradine, lomitapide, lovastatin, midazolam, omeprazole, oral anticoagulants (e.g. warfarin, rivaroxaban, apixaban), atypical antipsychotics (e.g. quetiapine), pimozide, quinidine, rifabutin, sildenafil, simvastatin, tacrolimus, terfenadine, triazolam and vinblastine, but this list is not comprehensive. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions.
Direct acting oral anticoagulants (DOACs): The DOACs dabigatran and edoxaban are substrates for the efflux transporter P-gp. Rivaroxaban and apixaban are metabolised via CYP3A4 and are also substrates for P-gp. Caution should be exercised when clarithromycin is co-administered with these agents particularly to patients at high risk of bleeding. See 7 WARNINGS AND PRECAUTIONS, General.
With certain drugs, co-administration of clarithromycin is contraindicated or should be avoided). (see Table 12).
Effects of Other Drugs on Clarithromycin
Clarithromycin is a substrate of CYP3A. Co-administration of strong inducers of the cytochrome
P450 metabolism system may accelerate the metabolism of clarithromycin and thus lower exposure to clarithromycin while increasing exposure to its metabolite 14-OH-clarithromycin which could impair the intended therapeutic effect. Furthermore, it might be necessary to monitor the plasma levels of the CYP3A inducer, which could be increased owing to the inhibition of CYP3A by clarithromycin (see also the relevant product information for the CYP3A4 inducer administered). Co-administration of potent CYP3A inhibitors may lead to increased exposure to clarithromycin and decreased exposure to its metabolite 14-OH-clarithromycin. Clarithromycin dosage adjustment or consideration of alternative treatments may be required.
Bi-Directional Drug Interactions
Bi-directional drug interactions are complex and may occur if both of the interacting drugs are substrates and inhibitors / inducers of CYP3A.
Additional Mechanisms
Interactions with clarithromycin have been reported with drugs metabolized by cytochrome P450 isoforms other than CYP3A system. Additional mechanisms, such as effects upon absorption, may also be responsible for interaction between drugs, including zidovudine and clarithromycin.
9.3 Drug-Behavioural Interactions
This information is not available for this drug product.
9.4 Drug-Drug Interactions
Some of the drug-drug interactions which have been reported between clarithromycin-macrolides and other drugs or drug categories are listed in Table 12.
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction. (i.e., those identified as contraindicated).
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Table 12 - Established or Potential Drug-Drug Interactions with Clarithromycin | ||||||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Concomitant Medication | Source of Evidence | Effect | Clinical Comments | |||||||
| Astemizole* / Terfenadine | CT | terfenadine-acid metabolite concentrations increase ↑ QT interval | Macrolides have been reported to alter the metabolism of terfenadine resulting in increased serum levels of terfenadine which has occasionally been associated with cardiac arrhythmias such as QT prolongation, ventricular tachycardia, ventricular fibrillation and torsades de pointes. See 2 CONTRAINDICATIONS. In a study involving 14 healthy volunteers, the concomitant administration of clarithromycin tablets and terfenadine resulted in a 2- to 3-fold increase in the serum levels of the acid metabolite of terfenadine, MDL 16, 455, and in prolongation of the QT interval. Similar effects have been observed with concomitant administration of astemizole and other macrolides. | |||||||
| Atazanavir | CT | ↑ clarithromycin levels ↑ atazanavir AUC | Both clarithromycin and atazanavir are substrates and inhibitors of CYP3A, and there is evidence of a bi-directional drug interaction. Co-administration of clarithromycin (500 mg twice daily) with atazanavir (400 mg once daily) resulted in a 2-fold increase in exposure to clarithromycin and a 70% decrease in exposure to 14-OH-clarithromycin, with a 28% increase in the AUC of atazanavir. Because of the large therapeutic window for clarithromycin, no dosage reduction should be necessary in patients with normal renal function. For patients with moderate renal function (creatinine clearance 30 to 60 mL/min), the dose of clarithromycin should be decreased by 50%. For patients with creatinine clearance < 30 mL/min, the dose of clarithromycin should be decreased by 75% using an appropriate clarithromycin formulation. Doses of clarithromycin greater than 1000 mg per day should not be co-administered with protease inhibitors. | |||||||
Atypical Antipsychotics (e.g., quetiapine) | Potential ↑ in concentrations of quetiapine and other atypical antipsychotics | Clarithromycin should not be used in combination with quetiapine unless clinically necessary. Due to CYP3A inhibition by clarithromycin, concentrations of quetiapine are expected to increase, which can result in serious and / or life-threatening adverse reactions, including malignant neuroleptic syndrome. For other atypical antipsychotic drugs (aripiprazole and risperidone) metabolized by CYP3A4, it is also recommended that concomitant administration with clarithromycin be avoided due to potential pharmacokinetic interactions. | ||||||||
Calcium Channel Blockers (e.g., verapamil, amlodipine, diltiazem) | C | Potential ↑ in verapamil concentrations | Caution is advised regarding the concomitant administration of clarithromycin and calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem) due to the risk of hypotension. Plasma concentrations of clarithromycin as well as calcium channel blockers may increase due to the interaction. Hypotension, bradyarrhythmias, and lactic acidosis have been observed in patients receiving concurrent verapamil, belonging to the calcium channel blockers drug class. | |||||||
| Carbamazepine | C | ↑ levels of carbamazepine | Clarithromycin administration in patients receiving carbamazepine has been reported to cause increased levels of carbamazepine. Blood level monitoring of carbamazepine should be considered. | |||||||
Cisapride* / Pimozide | C | ↑ levels of cisapride ↑ levels of pimozide | Elevated cisapride levels have been reported in patients receiving clarithromycin and cisapride concomitantly. This may result in QT prolongation and cardiac arrhythmias including ventricular tachycardia, ventricular fibrillation and torsade de pointes. Similar effects have been observed in patients taking clarithromycin and pimozide concomitantly. See 2 CONTRAINDICATIONS. | |||||||
| Colchicine | C | Potential colchicine toxicity | Colchicine is a substrate for both CYP3A and the efflux transporter, P-gp. Clarithromycin and other macrolides are known to inhibit CYP3A and P-gp. When clarithromycin and colchicine are administered together, inhibition of P-gp and/or CYP3A by clarithromycin may lead to increased exposure to colchicine. This risk may be further increased with concomitant medications metabolized by P-glycoprotein or strong CYP3A inhibitors. Concomitant use of clarithromycin and colchicine is contraindicated. See 2 CONTRAINDICATIONS. | |||||||
| Cyclosporine | C | ↑ levels of cyclosporine | There have been reports of elevated cyclosporine serum concentrations when clarithromycin and cyclosporine are used concurrently. Cyclosporine levels should be monitored and the dosage should be adjusted as necessary. Patients should also be monitored for increased cyclosporine toxicity. | |||||||
| Didanosine | CT | No change in didanosine pharmacokinetics in HIV-infected patients (n=12) | Simultaneous administration of clarithromycin tablets and didanosine to 12 HIV-infected adult patients resulted in no statistically significant change in didanosine pharmacokinetics. | |||||||
| Digoxin | C | ↑ levels of digoxin | Digoxin is thought to be a substrate for the efflux transporter, P-gp. Clarithromycin is known to inhibit P-gp. When clarithromycin and digoxin are administered together, inhibition of P-gp by clarithromycin may lead to increased exposure to digoxin. Elevated digoxin serum concentrations have been reported in patients receiving clarithromycin tablets and digoxin concomitantly. In post-marketing surveillance some patients have shown clinical signs consistent with digoxin toxicity, including potentially fatal arrhythmias. Serum digoxin levels should be carefully monitored while patients are receiving digoxin and clarithromycin simultaneously. | |||||||
Disopyramide / Quinidine | C | ↑ levels of disopyramide, resulting in ventricular fibrillation & QT prolongation (rarely reported) Torsades de pointes | Increased disopyramide plasma levels, resulting in ventricular fibrillation and QT prolongation, coincident with the co-administration of disopyramide and clarithromycin have rarely been reported. There have been post-marketed reports of torsades de pointes occurring with concurrent use of clarithromycin and quinidine or disopyramide. Electrocardiograms should be monitored for QTc prolongation during co-administration of clarithromycin with these drugs. Serum levels of these medications should be monitored during clarithromycin therapy. There have been post marketing reports of hypoglycemia with the concomitant administration of clarithromycin and disopyramide. Therefore blood glucose levels should be monitored during concomitant administration of clarithromycin and disopyramide. | |||||||
| Domperidone | C, T | ↑ levels of domperidone, resulting in QT prolongation and cardiac arrhythmias | Elevated domperidone levels have been reported in patients receiving a potent CYP3A4 inhibitor and domperidone concomitantly. This may result in QT prolongation and cardiac arrhythmias including ventricular tachycardia, ventricular fibrillation and torsades de pointes. Hence, co-administration of domperidone with QT-prolonging medicines and/or potent CYP3A4 inhibitors such as clarithromycin is contraindicated. See 2 CONTRAINDICATIONS. | |||||||
Ergot alkaloids Ergotamine / Dihydroergotamine | C | Potential ischemic reactions Potential ergot toxicity | Post-marketing reports indicate that co-administration of clarithromycin with ergotamine or dihydroergotamine has been associated with acute ergot toxicity characterized by severe peripheral vasospasm, dysesthesia, and ischemia of the extremities and other tissues including the central nervous system. Concomitant administration of clarithromycin and ergot alkaloids is contraindicated. See 2 CONTRAINDICATIONS. | |||||||
| Etravirine | CT | ↓ clarithromycin ↑14-OH-clarithromycin | Clarithromycin exposure was decreased by etravirine; however, concentrations of the active metabolite, 14- OH-clarithromycin, were increased. Because 14-OH-clarithromycin has reduced activity against Mycobacterium avium complex (MAC), overall activity against this pathogen may be altered; therefore alternatives to clarithromycin should be considered for the treatment of MAC. | |||||||
| Fluconazole | CT | ↑ clarithromycin Cmin & AUC | Concomitant administration of fluconazole 200 mg daily and clarithromycin 500 mg twice daily to 21 healthy volunteers led to increases in the mean steady-state clarithromycin Cmin and AUC of 33% and 18%, respectively. Steady-state concentrations of 14-OH-clarithromycin were not significantly affected by concomitant administration of fluconazole. No clarithromycin dose adjustment is necessary. | |||||||
HMG-CoA Reductase Inhibitors Lovastatin / Simvastatin Atorvastatin Rosuvastatin | C C | Rhabdomyolysis (rarely reported) | Concomitant use of clarithromycin with lovastatin or simvastatin is contraindicated (see 2 CONTRAINDICATIONS) as these statins are extensively metabolized by CYP3A4 and concomitant treatment with clarithromycin increases their plasma concentration, which increases the risk of myopathy, including rhabdomyolysis. Reports of rhabdomyolysis have been received for patients taking clarithromycin concomitantly with these statins. If treatment with clarithromycin cannot be avoided, therapy with lovastatin or simvastatin must be suspended during the course of treatment. See 7 WARNINGS AND PRECAUTIONS, HMG-CoA Reductase Inhibitors. Rare reports of rhabdomyolysis have also been reported in patients taking atorvastatin or rosuvastatin concomitantly with clarithromycin. Concurrent use of atorvastatin and clarithromycin may result in increased atorvastatin exposure. Caution should be exercised when prescribing clarithromycin with statins. In situations where the concomitant use of clarithromycin with statins cannot be avoided, it is recommended to prescribe the lowest registered dose of the statin. Use of a statin that is not dependent on CYP3A metabolism (e.g., fluvastatin) can be considered. Patients should be monitored for signs and symptoms of myopathy. | |||||||
| Itraconazole | CT, T | ↑ levels of clarithromycin ↑ levels of itraconazole | Both clarithromycin and itraconazole are substrates and inhibitors of CYP3A, leading to a bi-directional drug interaction. Clarithromycin may increase the plasma levels of itraconazole, while itraconazole may increase the plasma levels of clarithromycin. Patients taking itraconazole and clarithromycin concomitantly should be monitored closely for signs or symptoms of increased or prolonged pharmacologic effect. | |||||||
| ivabradine | T | Potential Increase in serum concentration | May significantly increase blood levels and effects of ivabradine; may lead to excessive bradycardia. See CONTRAINDICATION | |||||||
Lansoprazole / Omeprazole | CT | Mild change of lansoprazole and 14-OH-clarithromycin concentrations ↑ omeprazole Cmax & AUC0-24 ↑ levels of clarithromycin | One study demonstrated that concomitant administration of clarithromycin and lansoprazole resulted in mild changes of serum concentrations of lansoprazole and 14-OH-clarithromycin. However, no dosage adjustment is considered necessary based on these data. Clarithromycin 500 mg three times daily was given in combination with omeprazole 40 mg once daily to healthy subjects. The steady-state plasma concentrations of omeprazole were increased (i.e., Cmax, AUC0-24, and t1/2 increased by 30%, 89%, and 34%, respectively), by concomitant administration of clarithromycin. The mean 24-hour gastric pH value was 5.2 when omeprazole was administered alone and 5.7 when co- administered with clarithromycin. To a lesser extent, omeprazole administration increases the serum concentrations of clarithromycin. Omeprazole administration also increases tissue and mucus concentrations of clarithromycin. | |||||||
Oral Anticoagulants Warfarin / Acenocoumarol | C | ↑ anticoagulant effect | There have been reports of increased anticoagulant effect when clarithromycin and oral anticoagulants are used concurrently. Anticoagulant parameters should be closely monitored. Adjustment of the anticoagulant dose may be necessary. Clarithromycin has also been reported to increase the anticoagulant effect of acenocoumarol. There is a risk of serious hemorrhage and significant elevations in International Normalized Ratio (INR) and prothrombin time when clarithromycin is co-administered with warfarin. INR and prothrombin times should be frequently monitored while patients are receiving clarithromycin and oral anticoagulants concurrently. See 7 | |||||||
| WARNINGS AND PRECAUTIONS, Use with Other Drugs, Oral Anticoagulants. | ||||||||||
Oral Hypoglycemic Agents (e.g., Insulin) | C T | Hypoglycemia | The concomitant use of clarithromycin and oral hypoglycaemic agents (such as sulphonylurias) and/or insulin can result in significant hypoglycaemia. With certain hypoglycaemic drugs such as nateglinide, pioglitazone, repaglinide and rosiglitazone, inhibition of CYP3A enzyme by clarithromycin may be involved and could cause hypoglycaemia when used concomitantly. Careful monitoring of glucose is recommended. | |||||||
Phosphodiesterase inhibitors (e.g., sildenafil, tadalafil, vardenafil) | T | ↑ phosphodiesterase inhibitor exposure | Sildenafil, tadalafil, and vardenafil are metabolized, at least in part, by CYP3A, and CYP3A may be inhibited by concomitantly administered clarithromycin. Co-administration of clarithromycin with sildenafil, tadalafil or vardenafil would likely result in increased phosphodiesterase inhibitor exposure. Reduction of sildenafil, tadalafil and vardenafil dosages should be considered when these drugs are co-administered with clarithromycin. | |||||||
| Rifabutin | C | ↓ clarithromycin ↑ rifabutin | Clarithromycin has been reported to increase serum and tissue concentration of rifabutin and thus may increase the risk of toxicity. Clarithromycin levels decrease when co-administered with rifabutin. Concomitant administration of clarithromycin and rifabutin in the treatment of Mycobacterial Avium complex infections resulted in rifabutin-associated uveitis. A case control study in AIDS patients showed that concomitant administration of rifabutin and clarithromycin resulted in an approximately 50% reduction in serum clarithromycin concentration, approximately 77% increase in the area under the plasma concentration-time curve of rifabutin, and a 236% increase in the area under the plasma concentration-time curve of rifabutin’s active metabolite. The increase in rifabutin and/or its metabolite contributed to the development of uveitis (the incidence of uveitis was 14% in patients weighing >65 kg, 45% in patients between 55 and 65 kg, and 64% in patients <55 kg). | |||||||
Ritonavir / Indinavir | CT | ↑ clarithromycin Cmax, Cmin, & AUC | A pharmacokinetic study demonstrated that the concomitant administration of ritonavir 200 mg every 8 hours and clarithromycin 500 mg every 12 hours resulted in a marked inhibition of the metabolism of clarithromycin. The clarithromycin Cmax increased by 31%, Cmin increased 182% and AUC increased by 77% with concomitant administration of ritonavir. An essentially complete inhibition of the formation of 14-[R]-hydroxy-clarithromycin was noted. Because of the large therapeutic window for clarithromycin, no dosage reduction should be necessary in patients with | |||||||
↑ indinavir AUC ↑ clarithromycin AUC | normal renal function. However, for patients with renal impairment, the following dosage adjustments should be considered: For patients with creatinine clearance 30 to 60 mL / min the dose of clarithromycin should be reduced by 50%. For patients with creatinine clearance < 30 mL/min the dose of clarithromycin should be decreased by 75%. Doses of clarithromycin greater than 1g / day should not be co-administered with ritonavir. Similar dose adjustments should be considered in patients with reduced renal function when ritonavir is used as a pharmacokinetic enhancer with other HIV protease inhibitors including atazanavir and saquinavir. One study demonstrated that the concomitant administration of clarithromycin and indinavir resulted in a metabolic interaction; the clarithromycin AUC increased by 53% and the indinavir AUC was increased by 20%, but the individual variation was large. No dose adjustment is necessary with normal renal function. | |||||||||
| Saquinavir | CT | ↑ saquinavir AUC and Cmax ↑ clarithromycin AUC | Both clarithromycin and saquinavir are substrates and inhibitors of CYP3A, and there is evidence of a bi-directional drug interaction. Concomitant administration of clarithromycin (500 mg twice daily) and saquinavir (soft gelatin capsules, 1200 mg three times daily) for 7 days to 12 healthy volunteers resulted in steady-state AUC and Cmax values of saquinavir which were 177% (108-269%) and 187% (105-300%) higher than those seen with saquinavir alone. Clarithromycin AUC and Cmax values were approximately 40% higher than those seen with clarithromycin alone. [Clarithromycin AUC ↑ 45% (17-81%) and Cmax ↑ 39% (10-76%); 14-OH clarithromycin metabolite AUC ↓ 24% (5-40%) and Cmax ↓ 34% (14-50%)]. QTc prolongation has been reported in patients taking saquinavir along with ritonavir and also in patients taking clarithromycin. Concurent administration of saquinavir and clarithromycin is contraindicated (see 2 CONTRAINDICATIONS). | |||||||
| Tacrolimus | T | Potential ↑ in tacrolimus concentrations | Concomitant administration of tacrolimus and clarithromycin may result in increased plasma levels of tacrolimus and increased risk of toxicity. | |||||||
| Theophylline | T | Potential ↑ in theophylline concentrations | Clarithromycin use in patients who are receiving theophylline may be associated with an increase of serum theophylline concentrations. Monitoring of serum theophylline concentrations should be considered for patients receiving high doses of theophylline or with baseline concentrations in the upper therapeutic range. | |||||||
| Tolterodine | T | ↑ serum tolterodine concentrations | The primary route of metabolism for tolterodine is via the 2D6 isoform of cytochrome P450 (CYP2D6). However, in a subset of the population devoid of CYP2D6, the identified pathway of metabolism is via CYP3A. In this population subset, inhibition of CYP3A results in significantly higher serum concentrations of tolterodine. A reduction of tolterodine dosage may be necessary in the presence of CYP3A inhibitors, such as clarithromycin in the CYP2D6 poor metabolizer population. | |||||||
Triazolobenzo-diazepines (e.g., triazolam, alprazolam) Other related benzodiazepines (e.g., midazolam) | CT, C, T | ↑ midazolam AUC | When midazolam was co-administered with clarithromycin tablets (500 mg twice daily), midazolam AUC was increased 2.7-fold after intravenous administration of midazolam and 7-fold after oral administration. Concomitant administration of oral midazolam and clarithromycin is contraindicated. See 2 CONTRAINDICATIONS. If intravenous midazolam is co-administered with clarithromycin, the patient must be closely monitored to allow dose adjustment of midazolam. A drug-drug interaction study between oromucosal midazolam and clarithromycin has not been conducted. The same precautions should also apply to other benzodiazepines that are metabolized by CYP3A, including triazolam and alprazolam. For benzodiazepines which are not dependent on CYP3A for their elimination (temazepam, nitrazepam, lorazepam), a clinically important interaction with clarithromycin is unlikely. There have been post-marketing reports of drug interactions and central nervous system (CNS) effects (e.g., somnolence and confusion) with the concomitant use of clarithromycin and triazolam. Monitoring the patient for increased CNS pharmacological effects is suggested. | |||||||
| Zidovudine | C | Potential ↓ in zidovudine concentrations | Simultaneous oral administration of clarithromycin tablets and zidovudine to HIV-infected adult patients may result in decreased steady-state zidovudine concentrations. Clarithromycin appears to interfere with the absorption of simultaneously administered oral zidovudine, and therefore, this interaction can be largely avoided by staggering the doses of clarithromycin and zidovudine. This interaction does not appear to occur in pediatric HIV-infected patients taking clarithromycin suspension with zidovudine or dideoxyinosine. Similar interaction studies have not been conducted with clarithromycin extended-release (ER) and zidovudine. | |||||||
Other drugs metabolized by CYP3A (e.g., alfentanil, bromocriptine, cilostazol, methylprednisolone, vinblastine) | C, T | Potential increase in serum concentration | Interactions with erythromycin and / or clarithromycin have been reported with a number of other drugs metabolized by CYP3A, such as alfentanil, bromocriptine, cilostazol, ibrutinib, methylprednisolone, or vinblastine. Serum concentrations of drugs metabolized by CYP3A should be monitored closely in patients concurrently receiving erythromycin or clarithromycin. | |||||||
Other drugs metabolized by cytochrome P450 isoforms other than CYP3A (e.g., hexobarbital, phenytoin, and valproate) | C, T | Potential change in serum concentration | Interactions with erythromycin and / or clarithromycin have been reported with drugs metabolized by other cytochrome P450 isoforms (i.e., not CYP3A), such as hexobarbital, phenytoin, and valproate. Serum concentrations of these drugs should be monitored closely in patients concurrently receiving erythromycin or clarithromycin. | |||||||
Other drug inducers of the cytochrome P450 system (e.g, efavirenz, nevirapine, rifampin, rifabutin, rifampicin, phenobarbital, rifapentine) | CT, T | ↓ levels of clarithromycin | Strong inducers of the cytochrome P450 metabolism system such as efavirenz, nevirapine, rifampin, rifabutin, rifampicin, phenobarbital and rifapentine* may accelerate the metabolism of clarithromycin and thus lower the plasma levels of clarithromycin, while increasing those of 14-OH-clarithromycin, a metabolite that is also microbiologically active. Since the microbiological activities of clarithromycin and 14-OH-clarithromycin are different for different bacteria, the intended therapeutic effect could be impaired during concomitant administration of clarithromycin and enzyme inducers. | |||||||
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical Interactions with other drugs have not been established. * not marketed in Canada. | ||||||||||
Combination Therapy with Omeprazole and / or Amoxicillin
For more information on drug interactions for omeprazole and amoxicillin, refer to their respective Product Monographs, under 9 DRUG INTERACTIONS.
9.5 Drug-Food Interactions
SPC-Clarithromycin for Oral Suspension may be given with or without meals. Interactions with food have not been established.
9.6 Drug-Herb Interactions
St. John’s Wort (Hypericum perforatum) is an inducer of CYP3A and may induce the metabolism of clarithromycin. This may result in sub-therapeutic levels of clarithromycin leading to reduced efficacy.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
General
Clarithromycin exerts its antibacterial action by binding to the 50S ribosomal subunit of susceptible bacteria and suppressing protein synthesis.
10.3 Pharmacokinetics
Clarithromycin for Oral Suspension
A summary of clarithromycin pharmacokinetic parameters in adult volunteers following the administration of clarithromycin for oral suspension is provided in Table 13. See 10 CLINICAL PHARMACOLOGY, Detailed Pharmacology.
| Table 13 - Clarithromycin Pharmacokinetic Parameters in Adult Subjects following the Administration of Clarithromycin for Oral Suspension | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| 250 mg / 10 mL | Cmax (mg/L) | Tmax (hr) | t½ (hr) | AUC0-∞ (mg⋅hr/L) | |||||
Mean* (fasting conditions) | 1.24 | 3.3 | 3.7 | 7.2 | |||||
Mean* (fed conditions) | 0.95 | 5.3 | 3.7 | 6.5 | |||||
| * from Table 23 | |||||||||
A summary of clarithromycin pharmacokinetic parameters in pediatric patients following the administration of clarithromycin for oral suspension is provided in Table 14. See 10 CLINICAL PHARMACOLOGY, Detailed Pharmacology.
| Table 14 - Clarithromycin Pharmacokinetic Parameters in Pediatric Patients following the Administration of Clarithromycin for Oral Suspension | ||||||
|---|---|---|---|---|---|---|
Cmax (mg/L) | tmax (hr) | AUC0-t (mg⋅hr/L) | ||||
Single Dose (125 mg/5 mL) | ||||||
Mean* (fasting conditions) | 3.59 | 3.1 | 10 | |||
Mean* (fed conditions) | 4.58 | 2.8 | 14.2 | |||
Multiple Doses (7.5 mg/kg b.i.d.) | ||||||
Mean* (fasting conditions) | 4.6 | 2.8 | 15.7 | |||
* from Table 23 Legend: b.i.d. = twice daily | ||||||
Absorption
Clarithromycin for Oral Suspension
Adult Volunteers
Single and multiple dose adult volunteer studies showed that the suspension formulation was not significantly different from the tablet formulation in terms of Cmax of clarithromycin and AUC, although the onset and / or rate of absorption of the suspension formulation was slower than that of the tablet. As with the tablet formulation, steady-state is achieved by the fifth dose of a 12 hour multiple-dose suspension regimen.
Children
In children taking 15 to 30 mg /kg / day in two divided doses, steady-state clarithromycin Cmax values generally ranged from 8 to 20 mcg/mL. Cmax values as high as 23 mcg / mL have been observed in HIV-infected pediatric patients taking 30 mg / kg /day in two divided doses. In children requiring antibiotic therapy, administration of 7.5 mg / kg q12h doses every 12 hours of clarithromycin as the suspension generally resulted in steady-state peak plasma concentrations of 3 to 7 mcg / mL for clarithromycin, and 1 to 2 mcg / mL for 14-OH-clarithromycin. In HIV-infected children taking 15 mg / kg every 12 hours, steady-state clarithromycin peak concentrations generally ranged from 6 to 15 mcg / mL. A single and multiple dose study conducted in pediatric patients showed that food leads to a slight delay in the onset of absorption, but does not affect the overall bioavailability of clarithromycin.
Clarithromycin and its 14-OH metabolite penetrate into middle ear effusion (MEE) of patients with secretory otitis media.
For adult patients, the bioavailability of 10 mL of the 125 mg / 5mL suspension is similar to a 250 mg tablet.
Distribution
Clarithromycin distributes readily into body tissues and fluids, and provides tissue concentrations that are higher than serum concentrations. Examples from tissue and serum concentrations are presented in Table 15.
| Table 15 - Representative Clarithromycin Tissue and Serum Concentrations Following the Administration of 250 mg b.i.d of Clarithromycin Film-Coated Tablets | ||||||
| Tissue Type | Concentrations | |||||
| Tissue (mcg/g) | Serum (mg/L) | |||||
Tonsil Lung Leukocytes* | 1.6 8.8 9.2 | 0.8 1.7 1.0 | ||||
* in vitro data. Legend: b.i.d. = twice daily | ||||||
Metabolism
Clarithromycin is principally excreted by the liver and kidney. The major metabolite found in urine is 14-OH-clarithromycin.
Elimination
At 250 mg twice daily, approximately 20% of an orally administered dose of clarithromycin film-coated tablet is excreted in the urine as the unchanged parent drug. The urinary excretion of unchanged clarithromycin is somewhat greater (approximately 30%) with 500 mg twice daily dosing. The renal clearance of clarithromycin is, however, relatively independent of the dose size and approximates the normal glomerular filtration rate. The major metabolite found in urine is 14-OH-clarithromycin which accounts for an additional 10 to 15% of the dose with twice daily dosing at either 250 mg or 500 mg. Most of the remainder of the dose is eliminated in the feces, primarily via the bile. About 5 to 10% of the parent drug is recovered from the feces. Fecal metabolites are largely products of N-demethylation, 14-hydroxylation or both.
Special Populations and Conditions
Pediatrics
See 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Absorption.
Geriatrics
Dosage adjustment should be considered in elderly with severe renal impairment. In a steady-state study in which healthy elderly subjects (age 65 to 81 years old) were given 500 mg of clarithromycin every 12 hours, the maximum concentrations of clarithromycin and 14-OH-clarithromycin were increased. The AUC was also increased. These changes in pharmacokinetics parallel known age-related decreases in renal function. In clinical trials, elderly patients did not have an increased incidence of adverse events when compared to younger patients.
Hepatic Insufficiency
The steady-state concentrations of clarithromycin in subjects with impaired hepatic function did not differ from those in normal subjects; however, the 14-OH-clarithromycin concentrations were lower in the hepatically impaired subjects. The decreased formation of 14-OH-clarithromycin was at least partially offset by an increase in renal clearance of clarithromycin in subjects with impaired hepatic function when compared to healthy subjects. See 7 WARNINGS AND PRECAUTIONS, Hepatic /Biliary / Pancreatic and 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
Renal Insufficiency
The elimination of clarithromycin was impaired in patients with impaired renal function. The daily dose of clarithromycin should be limited to 500 mg in patients with severe renal impairment (creatinine clearance < 30 mL/min). See 7 WARNINGS AND PRECAUTIONS, Renal and 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment.
Detailed Pharmacology
Pharmacokinetics
Pharmacokinetics for clarithromycin and 14-OH-clarithromycin metabolite following the oral administration of a single dose or multiple doses of clarithromycin are outlined below.
Clarithromycin and Omeprazole
A pharmacokinetic study was conducted with clarithromycin 500 mg three times daily and omeprazole 40 mg once daily. When clarithromycin was given alone at 500 mg every 8 hours, the mean steady-state Cmax value was approximately 31% higher and the mean Cmin value was approximately 119% higher than when clarithromycin is compared with a previous study at 500 mg every 12 hours. The mean AUC0-24 for clarithromycin was 65% greater when 500 mg clarithromycin was given every 8 hours rather than every 12 hours. Neither Tmax nor half-life values appeared substantially different between the every-8-hour and every-12-hour regimens.
When clarithromycin was administered with omeprazole, increases in omeprazole half-life and AUC0-24 were observed. For all subjects combined, the mean omeprazole AUC0-24 was 89% greater and the harmonic mean for omeprazole t½ was 34% greater when omeprazole was administered with clarithromycin than when omeprazole was administered alone. When clarithromycin was administered with omeprazole, the steady-state Cmax, Cmin, and AUC0-8 of clarithromycin were increased by 10%, 27%, and 15%, respectively over values achieved when clarithromycin was administered with placebo.
At steady-state, clarithromycin gastric mucus concentrations 6 hours post dosing were approximately 25-fold higher in the clarithromycin/omeprazole group compared with the clarithromycin alone group. Six hours post-dosing, mean clarithromycin gastric tissue concentrations were approximately 2-fold higher when clarithromycin was given with omeprazole than when clarithromycin was given with placebo.
Clarithromycin distributes readily into body tissues and fluids, and provides tissue concentrations that are higher than serum concentrations. Examples from tissue and serum concentrations are presented in Table 16.
| Table 16 Representative Clarithromycin Tissue and Serum Concentrations | |||||||
| Tissue Type | Concentrations (after 250 mg b.i.d.) | ||||||
| Tissue (mcg/g) | Serum (mcg/mL) | ||||||
Tonsil Lung Leukocytes* | 1.6 8.8 9.2 | 0.8 1.7 1.0 | |||||
* in vitro data. Legend: b.i.d. = twice daily | |||||||
Clarithromycin for Oral Suspension
Adults
Plasma concentrations of clarithromycin and 14-OH-clarithromycin were studied in 17 healthy male adult volunteers following the administration of clarithromycin granules for suspension. A single phase dose was followed by the multiple dose phase. During the single dose phase, an oral 250 mg (10 mL) dose of clarithromycin granules for suspension was administered. Doses were administered in a fasting state (2 hours before breakfast after an overnight fast and 2 hours after dinner). Mean plasma concentrations of clarithromycin and 14-OH-clarithromycin are illustrated in Figure 1.
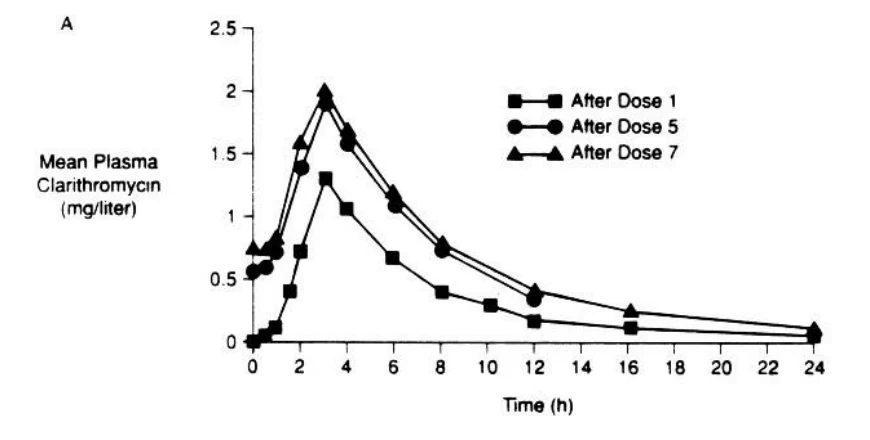
Figure 1: Mean Plasma Clarithromycin (A) and 14-OH-Clarithromycin (B) Concentration of Single and Multiple (Every 12-hours) Dose Administration(s) of 250 mg of Clarithromycin
A summary of pharmacokinetic parameters is presented in Table 17. After a single- and multiple-dose administration of clarithromycin as a suspension formulation, times to attain peak plasma clarithromycin and 14-OH-clarithromycin concentrations were prolonged, as evidenced by mean Tmax values ranging from 2.8 to 3.2 and 2.9 to 3.4 hours, respectively. Steady-state was achieved by Dose 5.
| Table 17 Clarithromycin and 14-OH-Clarithromycin Pharmacokinetic Parameters | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Parameters | Single Dose Mean ± SD | 5th Dose Mean ± SD | 7th Dose Mean ± SD | Comparison1 | ||||||||
| 1 vs 5 | 5 vs 7 | |||||||||||
| Clarithromycin | ||||||||||||
| Cmax (mcg/mL) | 1.34 ± 0.37 | 1.98 ± 0.55 | 2.15 ± 0.62 | * | NS | |||||||
| Tmax (hr) | 3.2 ± 1.1 | 2.8 ± 0.6 | 3.1 ± 0.9 | -- | -- | |||||||
| Cmin (mcg/mL) | 0.17 ± 0.10 | 0.32 ± 0.22 | 0.39 ± 0.25 | * | * | |||||||
| AUC2 (mcg⋅hr/mL) | 7.80 ± 2.87 | 11.5 ± 4.6 | 12.7 ± 4.8 | * | NS | |||||||
| t½3 (hr) | 3.6 | 3.2 | 3.5 | -- | -- | |||||||
| fu (% of dose) | -- | 36.9 ± 11.1 | 40.0 ± 14.0 | -- | NS | |||||||
| 14-OH-Clarithromycin | ||||||||||||
| Cmax (mcg/mL) | 0.46 ± 0.16 | 0.67 ± 0.15 | 0.72 ± 0.16 | * | NS | |||||||
| Tmax (hr) | 3.4 ± 1.2 | 2.9 ± 1.0 | 3.0 ± 1.0 | -- | -- | |||||||
| Cmin (mcg/mL) | 0.14 ± 0.04 | 0.23 ± 0.07 | 0.27 ± 0.07 | * | * | |||||||
| AUC2 (mcg⋅hr/mL) | 4.87 ± 1.24 | 5.33 ± 1.20 | 5.85 ± 1.17 | * | * | |||||||
| t½3 (hr) | 7.2 | 4.9 | 6.4 | -- | -- | |||||||
| fu (% of dose) | -- | 17.1 ± 3.1 | 18.4 ± 5.0 | -- | NS | |||||||
| ||||||||||||
Pediatric Patients
Children with pharyngitis, otitis media or skin infections
Another study was conducted in pediatric patients and included again both a single dose phase (2 groups, non-fasting and fasting) and multiple dose phase (1 group, fasting) design. It was conducted in 28 infants and children ages 6 months to 10 years with pharyngitis, otitis media or skin infections. The single dose phase involved the administration of a single 7.5 mg/ kg dose of clarithromycin granules for suspension (125 mg / 5 mL) in either a non-fasting or fasting (2 hours before or 1.5 hours after eating) state.
In the multiple dose phase, patients were given multiple 7.5 mg / kg doses (every 12 hours for 4 or 5 days) of clarithromycin granules for suspension in a fasting state.
A summary of pharmacokinetic parameters is presented in Table 18.
| Table 18 Clarithromycin and 14-OH-Clarithromycin Pharmacokinetic Parameters in Pediatric Patients | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Parameters | Single Dose Fasting Mean ± SD | Single Dose Non-Fasting Mean ± SD | 9th Dose b.i.d. Fasting Mean ± SD | |||||||||
| (Group I) | (Group III) | (Group II) | ||||||||||
| Clarithromycin | ||||||||||||
| Cmax (mcg/mL) | 3.59 ± 1.47 | 4.58 ± 2.76 | 4.60 ± 2.08 | |||||||||
| Tmax (hr) | 3.1 ± 1.0 | 2.8 ± 0.7 | 2.8 ± 1.0 | |||||||||
| Cmin (mcg/mL) | -- | -- | 1.67 ± 1.44 | |||||||||
| Lag (hr) | 0.6 | 0.4 | -- | |||||||||
| AUC6 (mcg⋅hr/mL) | 10.0 ± 5.49 | 14.2 ± 9.39 | 15.7 ± 6.72 | |||||||||
| 14-OH-Clarithromycin | ||||||||||||
| Cmax (mcg/mL) | 1.19 ± 0.37 | 1.26 ± 0.46 | 1.64 ± 0.75 | |||||||||
| Tmax (hr) | 3.2 ± 1.0 | 4.0 ± 1.0 | 2.7 ± 1.7 | |||||||||
| Cmin (mcg/mL) | -- | -- | 1.08 ± 0.84 | |||||||||
| Lag (hr) | 0.6 | 0.7 | -- | |||||||||
| AUC6 (mcg⋅hr/mL) | 3.66 ± 1.49 | 4.37 ± 1.79 | 6.69 ± 2.97 | |||||||||
Mean peak plasma clarithromycin and 14-OH metabolite concentrations after single dose administration in a fasting state were 3.59 and 1.19 mg /L, respectively. The differences in Cmax and AUC in the non-fasting and fasting group were not statistically significant. The study shows no deleterious effect of food co-administration on clarithromycin bioavailability in infants and children, similar to results previously noted in adults receiving the tablet formulation.
Mean peak plasma clarithromycin and 14-OH-clarithromycin concentrations after multiple dose (every 12 hours for 4 to 5 days) administration of 7.5 mg /kg of clarithromycin suspension in a fasting state were 4.60 and 1.64 mg /L, respectively. These values compare favourably with those observed in adults after multiple oral dose administration of 250 and 500 mg of clarithromycin. Cmax and AUC increase after multiple dosing as compared with values after single dose administration which is also comparable with data obtained in adults. This indicates that there is no unusual accumulation in infant and children.
Children with secretory otitis media
Multiple oral doses of clarithromycin (7.5 mg / kg every 12 hours for 7 days) were administered to 31 children ages 2 to 12 years with a diagnosis of secretory otitis media. Clarithromycin serum and middle ear effusion (MEE) concentrations were 1.73 ± 1.21 (range 0.16 to 4.96) mg/L and 2.53 ± 2.31 (range 0.39 to 10.62) mg/kg, respectively. In 16 of 24 patients MEE concentrations equalled or exceeded those in serum. The ratio of MEE to serum concentration was 2.48 ± 3.57 (range 0.19 to 15.31).
14-OH-clarithromycin serum and MEE concentrations were 0.82 ± 0.32 (range 0.26 to 1.53) mg/L and 1.27 ± 0.99 (range 0.24 to 4.20) mg/kg, respectively (Table 19). In 14 of 24 patients MEE concentrations equalled or exceeded those in serum. The ratio of MEE to serum concentration was 1.73 ± 1.4 (range 0.25 to 5.87).
| Table 19 Clarithromycin Serum and Middle Ear Effusion Concentrations after clarithromycin 7.5 mg/kg q12 h for 5 doses | ||
|---|---|---|
| Analyte | Serum (mcg/mL) | Middle Ear Fluid (mcg/mL) |
| Clarithromycin | 1.7 | 2.5 |
| 14-OH-Clarithromycin | 0.8 | 1.3 |
When children (n=10) were administered a single oral dose of 7.5 mg/kg suspension, food increased mean plasma clarithromycin concentration from 3.6 (± 1.5) mcg/mL to
4.6 (± 2.8) mcg/mL and the extent of absorption from 10.0 (± 5.5) mcg•hr/mL to
14.2 (± 9.4) mcg•hr/mL.
Although the onset and/or rate of absorption from the suspension formulation is significantly slower than that of the tablet formulation, this is of little clinical relevance.
11 STORAGE, STABILITY AND DISPOSAL
Store dry powder at controlled room temperature 15° C to 30° C. Protect from light. After reconstitution, store between (15°C and 25°C) and use within 14 days. Do not refrigerate. Discard after 14 days. The graduated syringe used for dosage administration should be rinsed between uses. Do not leave syringe in bottle. Do not store reconstituted suspension in syringe.
12 SPECIAL HANDLING INSTRUCTIONS
There are no further special handling instructions for this product (see 11 STORAGE, STABILITY AND DISPOSAL).
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
Clarithromycin
Chemical name:
(3R*, 4S*, 5S*, 6R*, 7R*, 9R*, 11R*, 12R*, 13S*, 14R*)-4-[(2,6-dideoxy-3-C-methyl-3-0-methyl-alpha-L-ribo-hexopyranosyl)oxy]-14-ethyl-12,13- dihydroxy-7-methoxy-3,5,7,9,11,13-hexamethyl-6-[[3,4,6-trideoxy-3- (dimethylamino)-beta-D-xylo- hexopyranosyl]oxy]oxacyclotetradecane-2-10- dione.
Molecular formula and molecular mass:
C38H69NO13 , 748 g/mol
Structural formula:
Physicochemical properties:
Clarithromycin is a white to off-white crystalline powder. It is soluble in acetone, slightly soluble in dehydrated alcohol, in methanol and in acetonitrile, practically insoluble in water. Slightly soluble in phosphate buffer at pH values 2 to 5.
The partition coefficient of clarithromycin is influenced by the pH of the water phase and polarity of the organic phase. For octanol (dipole moment = 0.25): water, the partition co-efficient varies from 5.63 to 46.0 for pH water increases from 2 to 8. The melting point of clarithromycin is approximately 225°C.
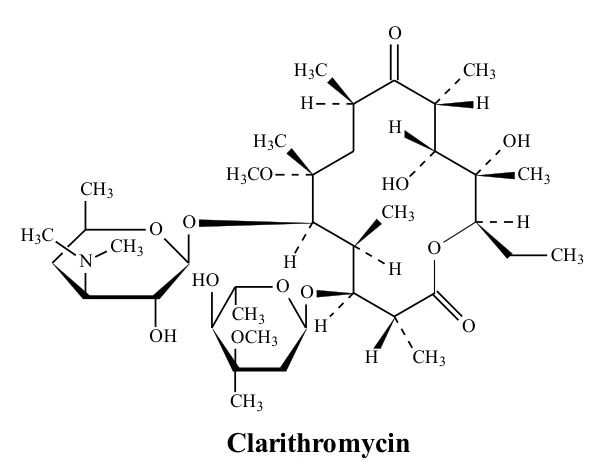
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
See 14 CLINICAL TRIALS, 14.2 Study Results - for trial design and study demographics by product and indication.
14.2 Study Results
Treatment of Mycobacterial Infections
Otitis Media:
In a controlled clinical study (317) of acute otitis media performed in the United States, where significant rates of beta-lactamase producing organisms were found, clarithromycin was compared to an oral cephalosporin. In a small number of patients, microbiologic determinations were made at the pre-treatment visit. Table 20 summarizes the presumptive bacterial eradications/clinical cure outcomes (i.e., clinical success). A summary of the study demographics and trial design is presented below.
| Table 20 - Summary of Demographics and Trial Design U.S. Acute Otitis Media Study Clarithromycin versus Oral Cephalosporin | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | ||||||
| 317 | Phase III, single-blind (investigator-blind), randomized, multicenter | clarithromycin suspension 7.5 mg/ kg/ dose (max 500 mg) b.i.d. cefaclor suspension 20 mg/kg (max 100 mg q.d.) b.i.d. | 379 patients | clarithromycin: 3.8 (0 to 13 years) cefaclor: 4.0 (0 to 12 years) | ||||||
| oral | ||||||||||
| 10 days | ||||||||||
| 497 | Phase III, single-blind (investigator-blind), randomized, multicenter | clarithromycin suspension 7.5 mg/ kg/ dose (max 500 mg) b.i.d. Augmentin suspension 13.3 mg/ kg/ dose of the amoxycillin component (max 500 mg) q8h | 433 | clarithromycin: 3.5 (0 to 12 years) Augmentin: 3.3 (0 to 12 years) | ||||||
| oral | ||||||||||
| 10 days | ||||||||||
| 649 | Phase III, single-blind (investigator-blind), randomized, multicenter | clarithromycin suspension 7.5 mg/ kg/ dose (max 500 mg) b.i.d. Augmentin suspension 13.3 mg/ kg/ dose of the amoxycillin component (max 500 mg) | 312 | Clarithromycin: 3.1 (6 months to 12 years) Augmentin: 3.5 (6 months to 12 years) | ||||||
| oral | ||||||||||
| 10 days | ||||||||||
| Legend: b.i.d. = twice daily; q8h = every 8 hours; q.d. = once daily | ||||||||||
| Table 21 - U.S. Acute Otitis Media Study Clarithromycin versus Oral Cephalosporin | |||
|---|---|---|---|
| Pathogen | Efficacy Results Outcome | ||
| S. pneumoniae | clarithromycin success rate, 13/15 (87%), control 4/5 | ||
| H. influenzae* | clarithromycin success rate, 10/14 (71%), control 3/4 | ||
| M. catarrhalis | clarithromycin success rate, 4/5, control 1/1 | ||
| S. pyogenes | clarithromycin success rate, 3/3, control 0/1 | ||
| Overall | clarithromycin success rate, 30/37 (81%), control 8/11 (73%) | ||
| * None of the H. influenzae isolated pre-treatment were resistant to clarithromycin; 6% were resistant to the control agent. | |||
The incidence of adverse events in all patients treated, primarily diarrhea (15% vs. 38%) and diaper rash (3% vs. 11%) in young children, was clinically or statistically lower in the clarithromycin arm versus the control arm.
In 2 other controlled clinical trials of acute otitis media performed in the United States, where significant rates of beta-lactamase producing organisms were found, clarithromycin was compared to an oral antimicrobial agent that contained a specific beta-lactamase inhibitor.
For the patients who had microbiologic determinations at the pre-treatment visit, Table 22 summarizes the presumptive bacterial eradication/clinical cure outcomes (i.e., clinical success).
| Table 22 Two U.S. Acute Otitis Media Studies Clarithromycin versus Antimicrobial/Beta-Lactamase Inhibitor | |||
|---|---|---|---|
| Pathogen | Efficacy Results Outcome | ||
| S. pneumoniae | clarithromycin success rate, 43/51 (84%), control 55/56 (98%) | ||
| H. influenzae* | clarithromycin success rate, 36/45 (80%), control 31/33 (94%) | ||
| M. catarrhalis | clarithromycin success rate, 9/10 (90%), control 6/6 | ||
| S. pyogenes | clarithromycin success rate, 3/3, control 5/5 | ||
| Overall | clarithromycin success rate, 91/109 (83%), control 97/100 (97%) | ||
| * Of the H. influenzae isolated pre-treatment, 3% were resistant to clarithromycin and 10% were resistant to the control agent. | |||
The incidence of adverse events in all patients treated, primarily diarrhea and vomiting, did not differ clinically or statistically for the 2 agents.
Appropriate culture and susceptibility tests should be performed prior to initiating treatment in order to isolate and identify organisms causing the infection and to determine their susceptibilities to clarithromycin. Therapy with clarithromycin may be initiated before results of these tests are known. However, modification of this treatment may be required once results become available or if there is no clinical improvement.
14.3 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of SPC-Clarithromycin for Oral Suspension 125 mg/5 mL (Sun Pharma Canada Inc.) with BIAXIN® 125 mg/5 mL (Abbott Laboratories Ltd., Canada) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from the 23 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clarithromycin (5 mL x 125 mg/5 mL) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 4022.00 4304.74 (39.4) | 4445.51 4637.90 (29.7) | 90.8 | 84.6 - 97.5 |
AUCI (ng·h/mL) | 4187.36 4480.88 (39.2) | 4597.58 4794.79 (29.6) | 91.4 | 85.2 - 98.2 |
Cmax (ng/mL) | 672.93 705.63 (34.5) | 782.21 808.30 (26.9) | 86.1 | 79.0 - 93.9 |
Tmax3 (h) | 3.15 (25.5) | 3.13 (22.9) | ||
T1/23 (h) | 4.32 (21.2) | 4.21 (16.8) | ||
1 SPC-Clarithromycin for Oral Suspension (clarithromycin for oral suspension), 125 mg/5 mL (Sun Pharma Canada Inc.)
2 BIAXIN® (clarithromycin for oral suspension), 125 mg / 5 mL (Abbott Laboratories Ltd., Canada)
3 Expressed as the arithmetic mean (CV%) only
A randomized, two-way, single-dose, crossover comparative bioavailability study of SPC-Clarithromycin for Oral Suspension 250 mg / 5 mL (Sun Pharma Canada Inc.) with BIAXIN® 250 mg / 5 mL (Abbott Laboratories Ltd., Canada) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from the 20 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clarithromycin (5 mL x 250 mg/5 mL) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (mcg·h/mL) | 12.52 13.46 (40.7) | 13.19 14.17 (40.8) | 94.9 | 87.8 - 102.6 |
AUCI (mcg·h/mL) | 12.97 13.90 (39.8) | 13.72 14.72 (40.4) | 94.6 | 87.7 - 101.9 |
Cmax (mcg/mL) | 1.79 1.86 (29.4) | 1.98 2.07 (31.6) | 90.5 | 81.9 - 100.0 |
Tmax3 (h) | 3.33 (2.00 – 4.33) | 3.17 (2.00 – 5.00) | ||
T1/24 (h) | 5.07 (15.5) | 5.10 (19.2) | ||
1 SPC-Clarithromycin for Oral Suspension (clarithromycin for oral suspension), 250 mg/5 mL (Sun Pharma Canada Inc.)
2 BIAXIN® (clarithromycin for oral suspension), 250 mg/5 mL (Abbott Laboratories Ltd., Canada)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
A randomized, two-way, single-dose, crossover comparative bioavailability study of SPC-Clarithromycin for Oral Suspension 250 mg/5 mL (Sun Pharma Canada Inc.) with BIAXIN® 250 mg/5 mL (Abbott Laboratories Ltd., Canada) was conducted in healthy, adult, male subjects under high-fat, high-calorie fed conditions. Comparative bioavailability data from the 36 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clarithromycin (5 mL x 250 mg/5 mL) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (mcg·h/mL) | 7.17 7.41 (25.68) | 7.99 8.48 (34.61) | 89.9 | 83.8 - 96.4 |
AUCI (mcg·h/mL) | 7.42 7.66 (25.19) | 8.26 8.75 (34.23) | 89.9 | 84.0 - 96.3 |
Cmax (mcg/mL) | 0.83 0.86 (27.97) | 0.94 1.00 (34.56) | 88.3 | 81.5 - 95.7 |
Tmax3 (h) | 5.67 (2.67 – 9.00) | 6.00 (2.67 – 10.00) | ||
T1/24 (h) | 5.35 (16.83) | 5.27 (18.02) | ||
1 SPC-Clarithromycin for Oral Suspension (clarithromycin for oral suspension), 250 mg/5 mL (Sun Pharma Canada Inc.)
2 BIAXIN® (clarithromycin for oral suspension), 250 mg/5 mL (Abbott Laboratories Ltd., Canada)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
Clarithromycin for Oral Suspension
Relative Bioavailability of Clarithromycin for Oral Suspension and Clarithromycin Tablet
Formulations
Plasma concentrations of clarithromycin and 14-OH-clarithromycin were studied in 22 healthy male adult volunteers following administration of single 250 mg oral doses of clarithromycin as granules for suspension or as a 250 mg immediate-release tablet. Each participant received 3 clarithromycin regimens:
Regimen A: 250 mg (10 mL) clarithromycin oral suspension under non-fasting conditions (30 min after the start of breakfast);
Regimen B: 250 mg (10 mL) clarithromycin oral suspension under fasting conditions (2 hours before breakfast after a minimum 12 hour overnight fast);
Regimen C: one 250 mg immediate-release tablet under fasting conditions (2 hours before breakfast after a minimum 12-hour overnight fast).
Mean plasma concentrations of clarithromycin and 14-OH-clarithromycin are illustrated in Figure 2.
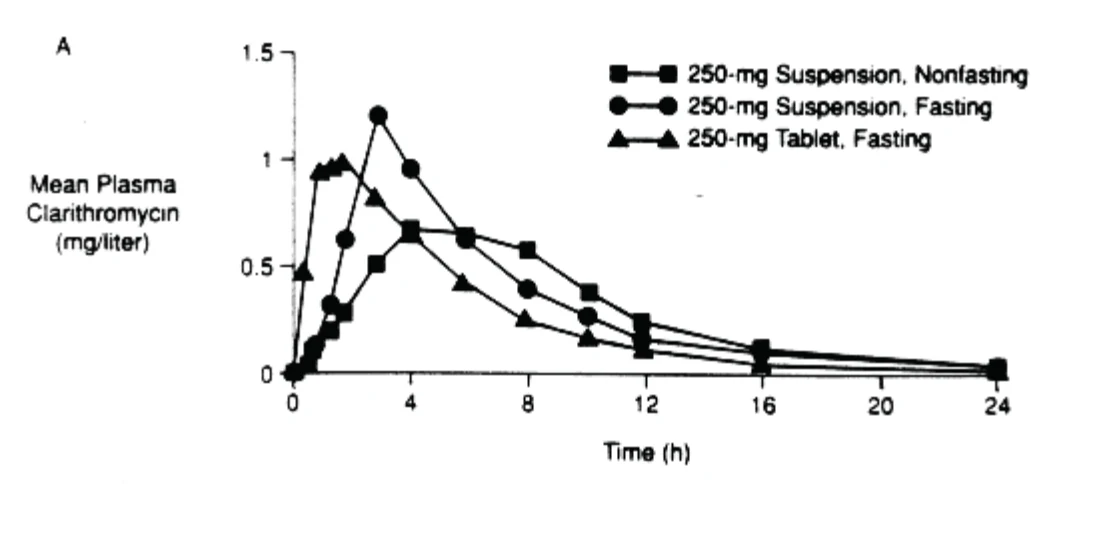
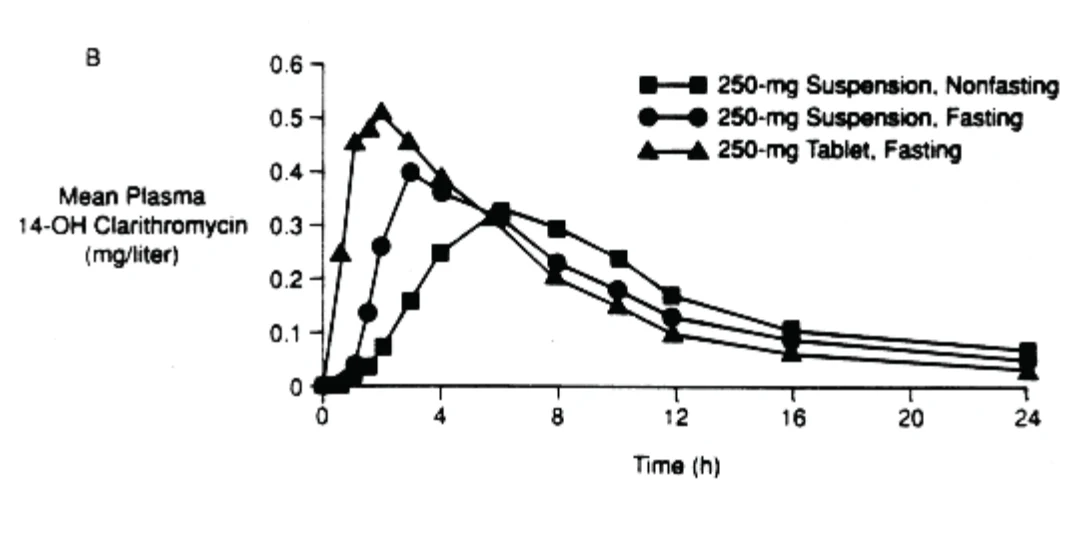
Figure 2: Mean Plasma Clarithromycin (A) and 14-OH-Clarithromycin (B) Concentration vs Time Data After Oral Administration of 250 mg of Clarithromycin
A summary of pharmacokinetic parameters is presented in Table 23.
The relative bioavailability of the oral suspension formulation compared with the tablet can be seen by comparing Regimen B versus Regimen C. The difference in clarithromycin Tmax (3.30 ± 1.20 vs.1.70 ± 0.60 hr) with the oral suspension and tablet formulations, respectively, shows that the onset and/or rate of absorption from the suspension is slower. A similar trend is seen with the 14-OH metabolite. For clarithromycin, Cmax was not significantly different between the formulations but for the 14 OH metabolite, Cmax after suspension administration was significantly lower than after tablet administration. The extent of absorption of clarithromycin was not significantly different from that of the tablet as assessed by AUC, whereas for the 14-OH metabolite, the tablet formulation was associated with a significantly higher extent of metabolite formation than the suspension formulation.
The difference between clarithromycin Tmax values under non-fasting and fasting conditions
| Table 23 - Comparative Single-Dose Bioavailability Data for Clarithromycin –Clarithromycin for Oral Suspension versus Clarithromycin Tablets 250 mg (IR Tablet) under Fasting Conditions and the Effect of Food on the Bioavailability of Clarithromycin for Oral Suspension | |||||||||||||||||||||
| Arithmetic Mean (CV%) | Relative Bioavailability | ||||||||||||||||||||
| Suspension Non-Fasting Regimen A | Suspension Fasting Regimen B | Tablet Fasting Regimen C | Point Estimate (%)+ | 90% Confidence Interval | |||||||||||||||||
| Clarithromycin | |||||||||||||||||||||
AUCτ (mcg·h / mL) | 6.52 (57) | 7.23 (35) | 6.33 (36) | A vs. B: 90.0 B vs. C: 114.0 | 77.5 – 102.4 99.8 – 128.2 | ||||||||||||||||
| Cmax (mcg/mL) | 0.95 (47) | 1.24 (29) | 1.10 (30) | A vs. B: 77.8 B vs. C: 112.1 | 63.8 – 91.8 96.4 – 127.8 | ||||||||||||||||
| Cmin (mcg/mL) | 5.3 (36) | 3.3 (35) | 1.7 (36) | -- | -- | ||||||||||||||||
| Tmax (hr) | 3.7 | 3.7 | 3.3 | -- | -- | ||||||||||||||||
| 14(R)-Hydroxy-Clarithromycin | |||||||||||||||||||||
AUCτ (mcg·h/mL) | 4.26 (35) | 4.65 (25) | 4.92 (29) | A vs. B: 91.1 B vs. C: 93.9 | 78.5 – 103.7 82.1 – 105.7 | ||||||||||||||||
| Cmax (mcg/mL) | 0.38 (30) | 0.42 (34) | 0.55 (32) | A vs. B: 90.4 B vs. C: 76.1 | 77.3 – 103.5 66.1 – 86.0 | ||||||||||||||||
| Tmax (hr) | 5.8 (27) | 3.4 (36) | 1.9 (30) | -- | -- | ||||||||||||||||
| t1/2 (hr) | 6.7 | 7.9 | 6.9 | -- | -- | ||||||||||||||||
Regimen A = 250 mg (10 mL) clarithromycin oral suspension under non-fasting conditions (30 min after the start of breakfast). Regimen B = 250 mg (10 mL) clarithromycin oral suspension under fasting conditions (2 hours before breakfast after a minimum 12-hour overnight fast). Regimen C = 250 mg clarithromycin IR tablet under non-fasting conditions (30 min after the start of breakfast). * Harmonic mean half-life. + Antilogarithm of the difference (test minus reference) of the least squares means for logarithms. Legend: IR = immediate-release | |||||||||||||||||||||
(Regimens A and B) was 5.30 ± 1.90 versus 3.30 ± 1.20 hr, respectively, and was similar for 14-OH-clarithromycin (5.80 ± 1.60 vs. 3.40 ± 1.20 hr). Therefore, the onset and/or rate of absorption from the suspension formulation is slowed by the presence of food.
For clarithromycin, Cmax was significantly higher under fasting than under non-fasting conditions. The extent of absorption of clarithromycin and formation of 14-OH-clarithromycin were not significantly different between fasting and the non-fasting conditions as assessed using AUC.
Single- and multiple-dose adult volunteer studies have established that the suspension and tablet formulations have similar pharmacokinetics.
15 MICROBIOLOGY
Clarithromycin exerts its antimicrobial action by binding to the 50S ribosomal subunit of susceptible microorganisms resulting in inhibition of protein synthesis.
Clarithromycin is active in vitro against various aerobic and anaerobic gram-positive and gram-negative organisms as well as most MAC microorganisms. The in vitro activity of clarithromycin is presented in Table 24.
Additionally, the 14-OH-clarithromycin metabolite also has significant antimicrobial activity which may be additive to the activity of the parent compound. Against Haemophilus influenzae, 14-OH clarithromycin is twice as active as the parent compound in vitro. However, for MAC isolates, the 14-OH metabolite was 4 to 7 times less active than clarithromycin. The clinical significance of this activity against MAC is unknown.
Clarithromycin is bactericidal to H. pylori; this activity is greater at neutral pH than at acid pH.
The ranges of MICs of clarithromycin, 14-OH-clarithromycin metabolite and the MICs required to inhibit 50% (MIC50) and 90% (MIC90) of bacteria are presented in Table 25 and Table 26. Beta-lactamase production should not have any effect on clarithromycin activity.
Cross-resistance to azithromycin has been documented. Attention should be paid to the possibility of cross resistance between clarithromycin and other macrolide drugs, as well as lincomycin and clindamycin.
The in vitro data indicate enterobacteriaceae, pseudomonas species and other non-lactose fermenting gram negative bacilli are not sensitive to clarithromycin.
Clarithromycin has been shown to be active against most strains of the following micro- organisms both in vitro and in clinical infections (See 1 INDICATIONS)
| Aerobic Gram-Positive microorganisms | Aerobic Gram-negative microorganisms | Other microorganisms | Mycobacteria |
Staphylococcus aureus Streptococcus pneumoniae Streptococcus pyogenes | Haemophilus influenzae Haemophilus parainfluenzae Moraxella catarrhalis | Mycoplasma pneumoniae Chlamydia pneumoniae (TWAR) | Mycobacterium avium complex (MAC) consisting of: Mycobacterium avium Mycobacterium Intracellulare |
The following in vitro data are available, but their clinical significance is unknown. Clarithromycin exhibits in vitro activity against most strains of the following microorganisms; however, the safety and effectiveness of clarithromycin in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trials (See 15 MICROBIOLOGY, Tables 24-26 below):
| Aerobic Gram-positive microorganisms | Aerobic Gram-negative microorganisms | Anaerobic Gram-positive microorganisms | Anaerobic Gram-negative microorganisms | Campylobacter |
Streptococcus agalactiae Viridans group streptococci | Bordetella pertussis Pasteurella multocida | Clostridium perfringens Propionibacterium acnes | Bacteroides melaninogenicus | Campylobacter jejuni |
Table 24 In Vitro Susceptibility® of Strains of Gram-Positive and Gram-Negative Bacteria to Clarithromycin
| Microorganisms | Number of Strains | Cumulative % of Strains Inhibited at MIC (mg/L) | |||||||||||
| .031 | .062 | .125 | .250 | .500 | 1.00 | 2.00 | 4.00 | 8.00 | 16.0 | 32.0 | 64.0 | ||
| Gram Positive | |||||||||||||
| Staphylococcus aureus | 25 | - | 4 | 4 | 8 | 8 | 12 | 12 | 12 | 12 | 12 | 12 | 100 |
| methicillin resistant | |||||||||||||
| Staphylococcus aureus | 126 | - | 20 | 75 | 84 | 86 | 87 | 87 | 87 | 88 | 88 | 88 | 100 |
| methicillin susceptible | |||||||||||||
| All Staphylococcus aureus | 151 | - | 17 | 63 | 72 | 73 | 74 | 74 | 74 | 75 | 75 | 75 | 100 |
| Staphylococcus epidermidis | 59 | - | 18 | 37 | 42 | 44 | 45 | 47 | 50 | 50 | 54 | 54 | 100 |
| Other coagulase negative | 27 | - | 14 | 44 | 44 | 48 | 48 | 48 | 55 | 55 | 59 | 59 | 100 |
| staphylococcus | |||||||||||||
| Streptococcus pyogenes (GrA) | 48 | 89 | 91 | 93 | 97 | 97 | 97 | 100 | - | - | - | - | - |
| Enterococcus | 97 | 1 | 4 | 8 | 25 | 59 | 61 | 63 | 63 | 64 | 64 | 68 | 100 |
| Streptococcus pneumoniae | 26 | 38 | 84 | 84 | 84 | 100 | - | - | - | - | - | - | - |
| Streptococcus agalactiae (GrB) | 41 | 95 | 95 | 95 | 95 | 95 | 97 | 100 | - | - | - | - | - |
| Streptococcus viridans | 15 | 86 | 86 | 86 | 93 | 93 | 93 | 93 | 93 | 93 | 93 | 93 | 100 |
| Other β-hemolytic Streptococcus | 19 | 78 | 78 | 78 | 84 | 84 | 84 | 89 | 89 | 94 | 94 | 94 | 100 |
| Corynebacterium species | 11 | 27 | 45 | 54 | 63 | 63 | 63 | 81 | 81 | 90 | 100 | - | - |
| Listeria monocytogenes | 7 | 28 | 100 | - | - | - | - | - | - | - | - | - | |
| Gram Negative | |||||||||||||
| Neisseria gonorrhoeae | 39 | 23 | 35 | 64 | 100 | - | - | - | - | - | - | - | - |
| Haemophilus influenzae | 56 | 3 | 3 | 3 | 7 | 16 | 37 | 80 | 100 | - | - | - | - |
| Neisseria meningitides | 6 | - | 33 | 50 | 83 | 100 | - | - | - | - | - | - | - |
| Campylobacter species | 30 | - | 10 | 10 | 43 | 80 | 93 | 100 | - | - | - | - | - |
* MICs do not take into account the antimicrobial activity of the 14-OH-clarithromycin metabolite.
Table 25 In vitro Susceptibility of Different Bacteria to Clarithromycin
| Microorganisms | Number of strains | MIC (mg/L) | ||||||||||||
| Range | 50% | 90% | ||||||||||||
| Mycoplasma pneumoniae | 30 | ≤0.004-0.125 | ≤0.004 | ≤0.031 | ||||||||||
| Bordetella pertussis | 18 | ≤0.008-0.06 | ≤0.008 | 0.03 | ||||||||||
| Legionella pneumophila | 14 | 0.12-0.25 | 0.12 | 0.25 | ||||||||||
| Haemophilus influenzae | 22 | 2-8 | 4 | 8 | ||||||||||
| Moraxella catarrhalis | 17 | 0.03-0.25 | 0.06 | 0.25 | ||||||||||
| Chlamydia trachomatis | 11 | 0.002-0.008 | 0.004 | 0.008 | ||||||||||
| Neisseria gonorrhoea | 26 | 0.0625-4 | 0.125 | 0.5 | ||||||||||
| Mycobacterium avium | 30 | 4-32 | 8 | 16 | ||||||||||
| Mycobacterium avium-intracellulare | 124 | < 0.25-4 | 1 | 2 | ||||||||||
| Mycobacterium chelonae | 137 | -- | -- | 0.25 | ||||||||||
| Mycobacterium fortuitum | 86 | -- | 2.0 | >8.0 | ||||||||||
| Mycobacterium kansassi | 24 | ≤0.125-0.25 | ≤0.125 | 0.25 | ||||||||||
| Pasteurella multocida | 10 | 1.0-4 | 1.0 | 2.0 | ||||||||||
| Bacteriodes melaninogenicus | 12 | ≤0.125-0.2 | ≤0.125 | ≤0.125 | ||||||||||
| Clostridium perfringens | 10 | 0.25-0.5 | 0.5 | 0.5 | ||||||||||
Staphylococcus aureus (methicillin sensitive) | 20 | 0.06-0.25 | 0.17 | 0.24 | ||||||||||
| Streptococcus pyogenes | 10 | ≤0.06 | ≤0.06 | ≤0.06 | ||||||||||
| Chlamydia pneumoniae | 49 | 0.004-0.025 | 0.016 | 0.031 | ||||||||||
| Helicobacter pylori † | 13 | 0.03-0.06 | 0.03 | 0.03 | ||||||||||
† Hardy DJ, Hanson CW, Hensey DM, Beyer JM, Fernandes PB. Susceptibility of Campylobacter pylori to macrolides and fluoroquinolones. J Antimicrob Chemother 1988;22:631-636.
Table 26 In vitro Susceptibility of Different Bacteria to 14-OH-Clarithromycin
| Microorganisms | Number of strains | MIC (mg/L) | |||||||||
| Range | 50% | 90% | |||||||||
| Streptococcus pyogenes | 15 | 0.015-0.03 | 0.015 | 0.03 | |||||||
| Streptococcus pneumoniae | 13 | ≤0.004-0.015 | 0.008 | 0.015 | |||||||
| Streptococcus agalactiae | 15 | 0.03-0.06 | 0.06 | 0.06 | |||||||
| Listeria monocytogenes | 14 | 0.25-0.5 | 0.5 | 0.5 | |||||||
| Moraxella catarrhalis | 17 | 0.03-0.12 | 0.06 | 0.12 | |||||||
| Neisseria gonorrhoeae | 15 | 0.06-1 | 0.25 | 0.5 | |||||||
| Campylobacter jejuni | 12 | 0.25-2 | 0.5 | 2 | |||||||
| Legionella pneumophila | 14 | 0.12-0.5 | 0.25 | 0.5 | |||||||
| Haemophilus influenzae | 22 | 1-4 | 2 | 4 | |||||||
| Bordetella pertussis | 18 | ≤0.008-0.06 | 0.015 | 0.06 | |||||||
| Bacteroides fragilis | 10 | 0.5->128 | 1 | 1 | |||||||
| Clostridium perfringens | 10 | 0.5-0.5 | 0.5 | 0.5 | |||||||
| Propionibacterium acnes | 12 | 0.03->128 | 0.03 | 0.06 | |||||||
Clarithromycin Kill Kinetics Against Helicobacter pylori
Figure 3 illustrates the kill kinetics of clarithromycin and 14-OH-clarithromycin against H. pylori at 8 × MIC and at pH 8.0; and Figure 4 illustrates the kill kinetics of clarithromycin and amoxicillin against H. pylori at pH 6.5.
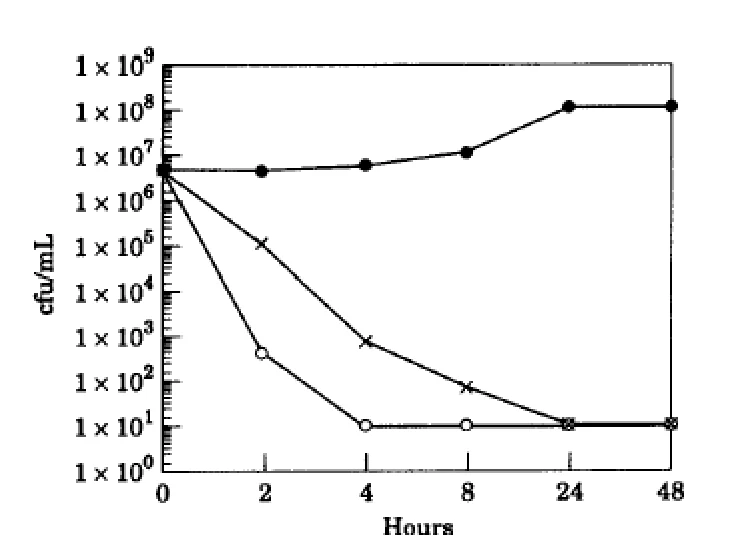
Figure 3: Kill kinetics of clarithromycin and 14-OH-clarithromycin against H. pylori strain 2597 at 8 × MIC and at pH 8.0. A flask was inoculated to produce a starting inoculum of approximately 106 cfu/mL. The flask was then incubated in an anaerobe jar with CampyPak® and shaken gently at 37°C. Counts were done at 0, 2, 4, 8, 24, and 48 h in physiological saline after 72 h incubation. ●, No antimicrobial; o, clarithromycin (0.12 mg/L); x, 14-OH-clarithromycin (0.24 mg/L).
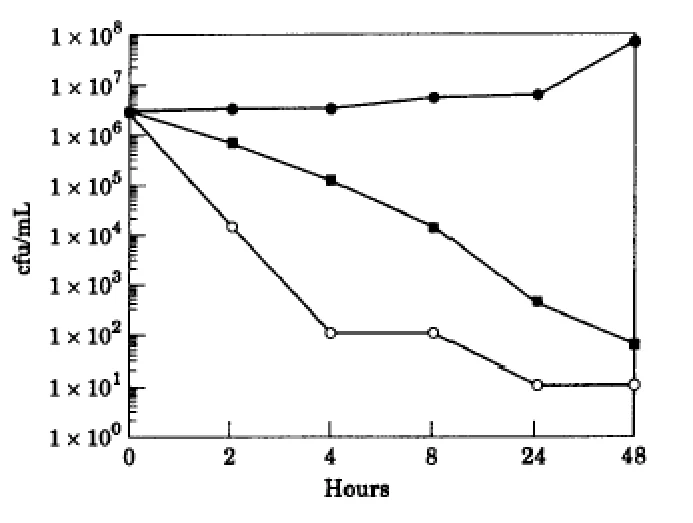
Figure 4: Kill kinetics of clarithromycin and amoxicillin against H. pylori strain 2597 at pH 6.5. Counts were done at 0, 2, 4, 8, 24, and 48 h in physiological saline after 72 h incubation. ●, No antimicrobial; o, clarithromycin (3 mg/L); ■, amoxicillin (3 mg/L)
Susceptibility Testing excluding Mycobacteria and Helicobacter
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimal inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a dilution method43 (broth or agar) or equivalent with standardized inoculum concentrations and standardized concentrations of clarithromycin powder.
The standard single disc susceptibility test (using the 15 mcg clarithromycin disc) and the dilution susceptibility test should be interpreted according to the criteria in Table 27.
| Table 27 - Criteria for the Interpretation of Standard Single Disc and Dilution Susceptibility Tests except for H. influenzae and H. pylori | |||||||
| Zone Diameter (mm) | Appropriate MIC Correlate (mg/L) | ||||||
| Susceptible | ≥ 18 | ≤ 2 | |||||
| Intermediate* | 14 to 17 | 4 | |||||
| Resistant | ≤ 13 | ≥ 8 | |||||
* Indicates that the test results are equivocal; therefore, dilution tests may be indicated. N.B. These criteria and the definition are in agreement with NCCLS. Documents M2-A644 and M100-S845. | |||||||
The standard single disc susceptibility test (using the 15 mcg clarithromycin disc) for H. Influenzae should be interpreted according to the criteria in Table 28.
| Table 28 - Criteria for the Interpretation of Standard Single Disc and Dilution Susceptibility Tests for H. influenzae | ||||||
| Zone Diameter (mm) | Appropriate MIC Correlate (mg/L) | |||||
| Susceptible | ≥ 13 | ≤ 8 | ||||
| Intermediate* | 11 to 12 | 16 | ||||
| Resistant | ≤ 10 | ≥ 32 | ||||
* Indicates that the test results are equivocal; therefore, dilution tests may be indicated. N.B. According to the revised NCCLS 1997 and 1998 Guidelines, the zone diameter and MIC values reflect both the activities of the parent compound and 14-OH metabolite. | ||||||
A report of "Susceptible" indicates that the pathogen is likely to respond to monotherapy with clarithromycin.
A report of "Intermediate" indicates that the result be considered equivocal, and if the microorganism is not fully susceptible to alternative clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where clarithromycin is physiologically concentrated or in situations where high clarithromycin dosages can be used. This category provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretations.
A report of "Resistant" indicates that achievable drug concentrations are unlikely to be inhibitory, and other therapy should be selected.
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure44 requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 15-mcg clarithromycin to test the susceptibility of microorganisms to clarithromycin.
Reports from the laboratory providing results of the standard single-disk susceptibility test with a 15-mcg clarithromycin disk should be interpreted according to the criteria in Table 27.
Standardized Dilution Techniques
Standardized susceptibility test procedures require the use of laboratory control microorganisms to control the technical aspects of the laboratory procedures. Standard clarithromycin powder should provide the following MIC values for S. aureus and H. influenzae (Table 29).
| Table 29 Standard Clarithromycin Powder MIC Values | |||||
| Microorganisms | MIC (mcg/mL) | ||||
| S. aureus | ATCC 29213 | 0.12 to 0.5 | |||
| H. influenzae | ATCC 49247 | 4 to 16 | |||
Standardized Diffusion Techniques
As with standardized dilution techniques, diffusion methods require the use of laboratory control microorganisms that are used to control the technical aspects of the laboratory procedures. For the diffusion technique, the 15-mcg clarithromycin disk should provide the following zone diameters for S. aureus and H. influenzae (Table 30).
| Table 30 Zone Diameter for the 15 mcg Clarithromycin Disc | ||||
| Microorganisms | Zone Diameter (mm) | |||
| S. aureus | ATCC 25923 | 26 to 32 | ||
| H. influenzae | ATCC 49247 | 11 to 17 | ||
In vitro Activity of Clarithromycin against Mycobacteria
Clarithromycin has demonstrated in vitro activity against MAC microorganisms isolated from both AIDS and non-AIDS patients. While gene probe techniques may be used to distinguish M. avium species from M. intracellulare, many studies only reported results on MAC isolates.
Various in vitro methodologies employing broth or solid media at different pH's, with and without oleic acid-albumin-dextrose-catalase (OADC), have been used to determine clarithromycin MIC values for mycobacterial species. In general, MIC values decrease more than 16-fold as the pH of Middlebrook 7H12 broth increases from 5.0 to 7.4. At pH 7.4, MIC values determined with Mueller-Hinton agar were 4- to 8-fold higher than those observed with Middlebrook 7H12 media. Utilization of OADC in these assays has been shown to further alter MIC values.
Clarithromycin activity against 80 MAC isolates from AIDS patients and 211 MAC isolates from non-AIDS patients was evaluated using a microdilution method with Middlebrook 7H9 broth. Results showed MIC values of ≤ 4.0 mcg/mL in 81% and 89% of the AIDS and non-AIDS MAC isolates, respectively. Twelve percent of the non-AIDS isolates had an MIC value ≤ 0.5 mcg/mL. Clarithromycin activity was evaluated against phagocytized MAC in mouse and human macrophage cell cultures as well as in the beige mouse infection model.
Clarithromycin activity was evaluated against Mycobacterium tuberculosis microorganisms. In 1 study utilizing the agar dilution method with Middlebrook 7H10 media, 3 of 30 clinical isolates had an MIC of 2.5 mcg/mL. Clarithromycin inhibited all isolates at > 10.0 mcg/mL.
Susceptibility Testing for Mycobacterium avium Complex
The disk diffusion and dilution techniques for susceptibility testing against gram-positive and gram-negative bacteria should not be used for determining clarithromycin MIC values against mycobacteria. In vitro susceptibility testing methods and diagnostic products currently available for determining MIC values against MAC organisms have not been standardized nor validated. Clarithromycin MIC values will vary depending on the susceptibility testing method employed, composition and pH of the media, and the utilization of nutritional supplements. Breakpoints to determine whether clinical isolates of M. avium or M. intracellulare are susceptible or resistant to clarithromycin have not been established.
In vitro Activity of Clarithromycin against Helicobacter pylori
Clarithromycin has demonstrated in vitro activity against H. pylori isolated from patients with duodenal ulcers. In vitro susceptibility testing methods (broth microdilution, agar dilution, E-test, and disk diffusion) and diagnostic products currently available for determining MICs and zone sizes have not been standardized, validated, or approved for testing H. pylori. The clarithromycin MIC values and zone sizes will vary depending on the susceptibility testing methodology employed, media, growth additives, pH, inoculum concentration tested, growth phase, incubation atmosphere, and time.
Susceptibility Test for Helicobacter pylori
In vitro susceptibility testing methods and diagnostic products currently available for determining MICs and zone sizes have not been standardized, validated, or approved for testing H. pylori microorganisms. MIC values for H. pylori isolates collected during 2 U.S. clinical trials evaluating clarithromycin plus omeprazole were determined by broth microdilution MIC methodology (Hachem CY et al., 1996). Results obtained during the clarithromycin plus omeprazole clinical trials fell into a distinct bimodal distribution of susceptible and resistant clarithromycin MICs.
If the broth microdilution MIC methodology published in Hachem CY et al., 1996 is used and the following tentative breakpoints are employed, there should be reasonable correlation between MIC results and clinical and microbiological outcomes for patients treated with clarithromycin plus omeprazole (Table 31).
| Table 31 Susceptibility Testing for Helicobacter pylori in Patients Treated with Clarithromycin and Omeprazole | ||||||
| MIC (mcg/mL) | Interpretation | |||||
| ≤ 0.06 | Susceptible (S) | |||||
| 0.12 to 2.0 | Intermediate (I) | |||||
| ≥ 4 | Resistant (R) | |||||
These breakpoints should not be used to interpret results obtained using alternative methods.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
The acute toxicity of clarithromycin administered by a variety of routes, was studied in mice and rats. The median lethal dose by the oral route ranged from 2.7 to > 5.0 g/ kg. Acute toxicity did not differ markedly between sexes (Table 32).
| Table 32 - Acute LD50 values of Clarithromycin | ||||||||
| Species | Sex | Route | LD50 value (g/ kg) | |||||
| Mice | M | p.o. | 2.74 | |||||
| F | p.o. | 2.7 | ||||||
| M | s.c. | > 5.0 | ||||||
| F | s.c. | > 5.0 | ||||||
| M | i.p. | 1.03 | ||||||
| F | i.p. | 0.85 | ||||||
| M | i.v. | 0.17 | ||||||
| F | i.v. | 0.2 | ||||||
| Rats | M | p.o. | 3.47 | |||||
| F | p.o. | 2.7 | ||||||
| M | s.c. | > 5.0 | ||||||
| F | s.c. | > 5.0 | ||||||
| M | i.p. | 6.69 | ||||||
| F | i.p. | 7.58 | ||||||
| Legend: i.p. = intraperitoneal; i.v. = intravenous; p.o. = oral; s.c. = subcutaneous | ||||||||
The primary signs of toxicity included reduction in activities, behaviours, weight gains, respiration rates and sedation. The emetic activity of clarithromycin prevented the determination of the lethal dose in dog.
The acute oral toxicity of clarithromycin in very young mice and rats was determined. The median lethal dose (1.2 g/ kg) was about 2-fold that seen in the older rodents.
Subchronic Toxicity
Studies were conducted in rats, dogs and monkeys with clarithromycin administered orally. The duration of administration ranged from 14 days to 42 days.
Rats
One study in rats (with oral doses up to 800 mg/ kg/ day) failed to show adverse effects in rats exposed to 50 mg/ kg/ day for 4 weeks. The clinical signs observed at toxic doses were reduced motility, piloerection, hypothermia and perineal urine staining. Changes occurred in biochemical parameters at 200 and 800 mg/ kg/ day indicative of hepatotoxicity which was confirmed by histopathologic findings of hepatocyte necrosis.
Other pathologic findings at the top 2 dose levels included swelling of the renal cortical tubular epithelia and atrophic changes to the lymphatic and genital systems. The same toxicity profile was observed in immature rats following the daily administration of oral doses up to 150 mg/kg/day of clarithromycin for 6 weeks. At 150 mg/ kg/ day, there was an increase in relative weights of liver and kidneys.
Dogs
Dogs were dosed orally with 0, 6.25, 25, 100 or 400 mg/ kg/ day of clarithromycin daily for 28 days. Emesis occurred sporadically in the treated dogs. No other adverse effects were seen in dogs exposed to 6.25 mg /kg /day. The clinical signs at higher dosages included loose stools, lacrimation and conjunctivitis.
Slight anorexia was noted in dogs receiving 100 mg /kg /day or more. Dogs at 400 mg /kg /day exhibited reduced red blood cell count, hematocrit, hemoglobin concentration, serum albumin, and mean urine pH and specific gravity. Increases were seen in serum transaminase, alkaline phosphatase, and total bilirubin concentrations.
Bilirubin was detected in the urine. Other pathologic changes at 400 mg/kg/day included biliary hyperplasia, gastric glandular atrophy, renal tubule epithelial atrophy, edema of the iris, ciliary body and choroid, capillary proliferation in the cornea, suppression of spermatogenesis, and adrenal medullary degeneration.
Monkeys
Monkeys were treated daily for 1 month with oral doses of 0, 25, 100 or 400 mg/kg/day. Two animals out of 10 receiving 400 mg/kg/day died. Salivation was recorded at all dosage levels. No other adverse effects were seen in animals treated daily with 25 mg / kg/day.
The clinical signs observed at higher doses and most frequently at 400 mg/kg/day were vomiting, emesis, sunken eyes, dehydration, emaciation, low rectal temperature, body weight loss, reduced food consumption, cloudiness of the cornea and reduction in intra-ocular pressure. Yellow discoloured feces were passed on a few isolated occasions by some animals given a dose of 400 mg/kg/day. As with the other species, the liver was the primary target at toxic doses as shown by early elevation of serum concentration of glucose, BUN, creatinine, ALT, AST, LDH, amylase and/or triglyceride; an electrolyte imbalance and low levels of protein, cholesterol, phospholipid; elevated leucine aminopeptidase (LAP).
Principal histopathologic changes were seen mainly in high dose monkeys, but some mid-dose monkeys exhibited similar alterations. Changes included necrosis and vacuolation of hepatocytes, vacuolation of renal cortical tubules, no spermatogenesis, thymic regression and single cell necrosis of the stomach. In man the recommended dose is 500 to 1000 mg/day or 7.1 to 14.3 mg/ kg/ day (70 kg person).
Chronic Toxicity
Rats (20/sex/group) were treated daily with oral doses of 0, 15, 37.5, 75 or 150 mg/kg/day for 3 months. There were 8 incidental deaths, but none of them were considered treatment related. Clinical signs included increased salivation, dehydration, hyperactivity and were observed in a dose-related manner. The only toxic effect noted, was some variation in body weight gain. No toxicologically significant changes occurred in hematology, biochemistry or urinalysis results.
Post mortem, there was an increase in mean relative liver and kidney weights at the top dose level. No microscopic changes were detected in the kidneys, but in the liver, there was a sex/dose-related increase in multinucleated hepatocytes. Effects were only seen in females at 150 mg/kg/day but in males occurred as low as 37.5 mg/kg/day.
A 6-month oral study was performed in rats (20 to 27/sex/group) at dosages of 0, 1 to 6, 8, 40 or 200 mg/kg/ day. Seven male and female rats from the control group and the 40 and 200 mg/kg/day groups were allowed a 63-day non-dosed recovery period. No mortalities occurred. Body weight and food intake were reduced at high doses during the dosing phase but normalized during recovery.
Water intake and urine volume increased in males and females of the 40 and 200 mg/ kg/day groups. Dose-related hematological changes included reduced erythrocytes and HCT with increased MCV, MCH and MCHC and relative eosinophil counts. Biochemical changes were mainly restricted to the high dose group and included increased ALP and decreased phospholipids; decreased total cholesterol and triglycerides, and increased AST and ALT in males only and decreased albumin in females only.
Organ weight increases were found to include cecum, adrenals, liver, and spleen. Histopathological examinations showed drug-related, recovery-reversible increases in multinucleated hepatocytes associated with minimal and focal necrosis in livers of both sexes at the top 2 dose levels. No relevant pathology was found in the cecum, adrenals or spleen to account for the increased weights. After recovery only the 200 mg/kg/day group had increased multinucleated hepatocytes.
Dogs (7/sex/group) were administered daily with oral doses of 0, 10, 30, or 100 mg/kg/day of clarithromycin for 3 months. Emesis occurred at levels of 30 mg/kg and above. One male high-dose dog was killed in extremis on day 69. Drug-related lesions were seen in the liver, gall bladder, thymus and stomach.
Hematological and biochemical changes at the high dose level included, decreased RBC and HCT, increased ALT, ALP, GGT, and decreased total protein and albumin. No significant organ weight changes were recorded, but treatment-related microscopic alterations in the liver and stomach of mild- and high-dose dogs were seen, as well as changes in gall bladder, spleen and thymus of high-dose animals.
A 6-month oral study was also performed in dogs (4 to 5/sex/group) at dosages of 0, 0.8, 4, 20 or 100 mg/kg/day. At the 0 and 100 mg/kg levels, 1 male and 1 female dog were allowed a 1-month, non-dosed, recovery period. One male-high dose dog died on day 174. This death was considered to be as a direct result of clarithromycin administration. Histopathologic examination revealed hepatic parenchymal damage, identifying the cause of clinical jaundice. Clinical signs during the dosing phase of the study were restricted to the top 2 dose levels and included emesis and ocular signs. Food consumption and water intake were reduced at 20 and 100 mg/kg/day.
Hematologic changes at 100 mg/kg were indicative of subclinical anemia. Biochemical alterations at the same level were associated with liver damage. Ocular changes were only apparent at the top dose level.
Increase in the weights of lung, liver, spleen, adrenals and kidneys were found at 100 mg/kg/day. Histopathologic examination of these organs showed degeneration of liver parenchyma, and toxic effects in adrenals. The thymus weight was reduced at 100 mg/kg/day. At the end of the recovery period all findings had regressed or reduced.
Monkeys (5 to 6 /sex /group) were similarly administered clarithromycin at levels of 0, 25, 50 or 100 mg/kg/day for 6 months. At the 0 and 100 mg/kg levels, 1 male and 1 female monkey were allowed a one-month recovery period. One high-dose female died in week 25. Inhalation of vomit was considered to be the cause of death. Clinical signs were restricted to a dose-related incidence of emesis and salivation. No treatment-related effects were found in food consumption, ophthalmoscopy or hematology. Weight loss was restricted to 1 high-dose female. Minor serum chemistry changes were seen at the 100 mg /kg level, particularly in plasma proteins. Urinalysis revealed a dose-related lowering of pH and SG at 13 weeks only. Organ weight increases in liver, adrenal and kidneys were seen at high doses, but pathology was restricted to minimal liver changes consisting of cytoplasmic rarefaction of centrilobular hepatocytes. All changes were reversed during the recovery period.
Carcinogenicity
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of clarithromycin.
Mutagenicity
The following in vitro mutagenicity tests have been conducted with clarithromycin: Salmonella/ mammalian microsome test, bacterial induced mutation frequency test, in vitro chromosome aberration test, rat hepatocyte DNA synthesis assay, mouse lymphoma assay, mouse dominant lethal study, mouse micronucleus test.
All tests had negative results except the in vitro chromosome aberration test which was weakly positive in one test and negative in another. In addition, a Bacterial Reverse-Mutation Test (Ames Test) has been performed on clarithromycin metabolites with negative results.
Reproductive and Developmental Toxicology:
Fertility and reproduction studies have shown that daily doses of 150 to160 mg/kg/day to male and female rats caused no adverse effects on the estrous cycle, fertility, parturition, or number and viability of offspring. Plasma levels in rats after 150 mg/kg/day were 2 times the human serum levels.
In the 150 mg/kg/day monkey studies, plasma levels were 3 times the human serum levels. When given orally after 150 mg/kg/day, clarithromycin was shown to produce embryonic loss in monkeys. This effect has been attributed to marked maternal toxicity of the drug at this high dose.
In rabbits, in utero fetal loss occurred at an intravenous dose of 33 mg/m2, which is 17 times less than the maximum proposed human oral daily dose of 618 mg/m2.
Special Toxicology:
Acute Renal Toxicity
There was no evidence of nephrotoxicity of clarithromycin in the rat at doses up to 500 mg/kg/day.
Hepatotoxicity
In the in vitro and in vivo hepatotoxicity studies comparing clarithromycin with erythromycin, it was found that clarithromycin caused no greater cytotoxicity than erythromycin stearate and much less toxicity than erythromycin estolate. Hepatic enzyme induction was not found in doses below 500 mg/kg/day. In cynomolgus monkeys, the closest metabolic model for humans, elevations of ALT and LDH were identified at 200 mg/kg/day.
In dogs, a rise of ALT has been seen at 100 mg/kg/day, and in Wistar rats, a similar elevation of enzymes was seen at 200 mg/kg/day. Morphologic lesions related to prolonged exposure to clarithromycin (up to 6 months) have been consistent with reportedly reversible changes in rat, dog and monkey studies. Such doses are many times beyond the therapeutic range in humans, which is within 8 to 10 mg/kg/day.
Ocular Toxicity
Ocular lesions appear confined to dogs and monkeys receiving lethal doses, which were large multiples of the human therapeutic dose. Radiolabelled clarithromycin studies indicate the eye is not selectively burdened by drug deposits and that clearance from this tissue follows that seen in other tissues. Opacities occur in the cornea following widespread extraocular tissue changes which are detectable via numerous diagnostic methods. Reduced intraocular pressure precedes corneal opacity in a relatively predictive manner. Some evidence for transient opacity and at least partial resolution was noted in animal studies, but most animals succumbed to other organ dysfunctions shortly after opacities were observed.
Animals given doses close to the therapeutic dose had no ocular changes. No ophthalmologic effects were noted in rabbits treated at doses of 40 and 160 mg/kg/day for 28 days.
Ototoxicity
No effects on pinna reflex were seen in guinea pigs at a dose of 400 mg/ kg/ day but inner and outer hair cells disappeared suggesting toxic damage. No evidence of damage was reported at 200 mg/ kg/ day.
Juvenile Toxicity:
Clarithromycin for Oral Suspension
Clarithromycin was administered orally to rats and mice 3 days after birth. The study design was 10M/ 10F animals in the dose groups, 20M/20F in the control group. The animals were dosed by gavage with a single dose of a suspension of clarithromycin in 5% gum arabic; control animals received a solution of 5% gum arabic. The recovery period was 14 days.
Mice
The mice were dosed at 714, 857, 1028, 1233, 1480 and 1776 mg/ kg; the rats at 769, 1000, 1300, 1690, 2197 and 3713 mg/ kg.
LD50 (95% confidence limits) in mice was 1290 mg/ kg (1170 to 1420 mg/ kg) in males and
1230 mg/kg (1130 to 1340 mg/kg) in females; the sex difference was considered to be negligible.
LD50 of clarithromycin orally administered to adult mice is about 2700 mg/kg; acute toxicity was more notable in juvenile animals than in adults. The LD50 of antibiotics of the penicillin group, cephalosporin group and macrolide group is generally lower in juvenile animals than in adults; clarithromycin showed similar results.
Body weight was reduced or its increase was suppressed in both males and females of each dosing group from 1 to 4, 7 or 9 days after the administration, but its changes thereafter were comparable to those in the control group.
Some animals died from 1 to 7 days after the administration. The general condition, suckling behaviour and spontaneous movements were depressed in some of the mice administered 1028 mg/ kg or more clarithromycin from 1 day after the administration, but these changes disappeared by 7 days after the administration in those that survived the observation period.
Necropsy of those that died spontaneously disclosed dark reddish lungs in more than half the animals. This finding suggests that the death in these animals was due to debilitation resulting from reduced suckling behaviour.
In the survivors, necropsy showed dilation of renal pelvis in 1 male of the 1028 mg/kg group and hypoplasia of the kidney in 1 female of the 1233 mg/ kg group, but these uncommon conditions are considered to be incidental.
Rats
LD50 (95% confidence limits) in rats was 1330 mg/kg (1210 to 1470 mg/ kg) in males and 1270 mg/kg (1150 to 1400 mg/kg) in females, the sex difference was considered to be negligible.
LD50 of the agent administered orally to adult rats is about 3000 mg/kg; the acute toxicity was more notable in juvenile animals than in adult animals. LD50 of antibiotics of the penicillin group, cephalosporin group, and macrolide group is generally lower in juvenile animals than in adult animals; clarithromycin showed similar results.
The body weight was reduced or its increase was suppressed in both males and females of each dosing group from 1 to 4 or 7 days after the administration, but body weight changes thereafter were comparable to those of the control group.
Some of the animals of both sexes died from 2 to 5 days after the administration. The general condition, suckling behaviour and spontaneous movements were depressed in some animals from 1 or 2 days after the administration, but in survivors these changes disappeared by 13 days after the administration. In the control group, 1 male and female of the same litter showed depressed suckling behaviour and spontaneous movements from 13 days after the administration, and the female was cannibalised by its mother 14 days after the administration. This is considered to be due to the death of all the other animals of the litter and a resultant reduction in the nursing activity of the mother.
Necropsy of those that died spontaneously showed dark-reddish lungs in about 25%. A reddish-black substance was noted in the intestines of a few males and females of each group administered 2197 mg/kg or more clarithromycin, probably because of bleeding from the intestines. From these findings, the deaths were considered to be due to debilitation resulting from depressed suckling behaviour or bleeding from the intestines.
Necropsy of the survivors revealed nodulated ribs in 1 male of the control group. Since this animal showed a reduction in body weight from 11 days after the administration, these nodules are considered to have been caused by suppressed development of the ribs associated with a delay in the growth. White spots in the liver surface of the 769 mg/kg and 1300 mg/kg groups, and a bulging mass on the surface of the liver and adhesion of the liver to the diaphragm were observed in 1 female of the 769 mg/kg group. Since these changes were infrequent and were not observed in the animals that died during the observation period, they are considered to be incidental.
Three clarithromycin pediatric formulations under consideration for development, a carbopol complex, a hot melt sprayed coating form and a spray-congealed dosage form, were evaluated for acute oral toxicity in rats. Five male and 5 females were administered a single oral dose of 1 of 3 clarithromycin pediatric formulations at a concentration of 250 mg/mL. The dose for all rats was 20 mL/kg (i.e., 5 g/ kg). Except for one rat considered to have been misdosed with the spray congealed dosage form, none of the rats died and no signs of toxicity were observed.
No gross morphologic changes were found when the rats were killed and necropsied 2 weeks after treatment.
Doses greater than 5 g/ kg were considered to be excessive (5 g/ kg is generally employed as the highest test dose for test materials with toxicity too low to determine the minimum lethal dose). Thus, clarithromycin pediatric formulations were found to be non-toxic to rats at the applicable maximum dose of 5 g/ kg.
Clarithromycin for Oral Suspension
Rats
Two-week toxicity study was done with clarithromycin granules administered orally to preweaning rats. Crl:CD*(SD)BR pups, 5 days old at the start of treatment, were dosed by oral gavage with suspension for 17 to 20 days (Table 33).
| Table 33 - Subchronic Toxicity Study with Clarithromycin Granules Administered Orally to Crl:CD*(SD)BR Preweaning Rats (17 to 20 Treatment Days) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Treatment Group | Test Material | Dosagesa (mg/kg/day) | Concentrationb( mg/mL) | No/Group | ||||||||
| M | F | |||||||||||
| T0 | Vehiclec | 0 | 0 | 10 | 10 | |||||||
| T1 | Clarithromycin Granule for Suspension | 15 | 2.46 | 10 | 10 | |||||||
| T2 | Clarithromycin Granule for Suspension | 55 | 9.02 | 10 | 10 | |||||||
| T3 | Clarithromycin Granule for Suspension | 200 | 32.79 | 10 | 10 | |||||||
a Dosages are expressed in terms of the free base. b In terms of bulk granule (a potency of 610 mcg/ mg). c 0.2% hydroxypropylmethylcellulose (HPMC). | ||||||||||||
One female pup in the vehicle Control group was found dead on day 18. Sporadic incidence of reddish spots on the skin or skin erythema occurred in some T3 pups. The mean weight gains from days 0 to 17 for T3 males and females were approximately 20 and 10% less than those of T0 males and females, respectively. There were no ophthalmic effects. Statistically significant decreases occurred in the values of mean hemoglobin, mean cell hemoglobin and mean cell volume of T3 male pups (200 mg/kg/day); T3 female pups (200 mg/ kg/ day) had lower hemoglobin and hematocrit values when compared to controls, but the differences were not significant; similarly the mean hematocrit value of the T3 male pups was also lower than that of the controls. A statistically significant increase was observed in the mean relative kidney weights of T3 pups when compared to controls. Treatment-related minimal to mild multifocal vacuolar degeneration of the intrahepatic bile duct epithelium and an increased incidence of nephritic lesions were observed in the T3 pups (200 mg/kg/day).
A dosage of 200 mg/ kg/ day for 2 weeks produced decreased body weight gain, decreased mean hemoglobin and hematocrit values as well as histopathologic changes in the livers and kidneys of preweaning rats. The "no-toxic-effect" dosage in this 2-week preweaning rat study was judged to be 55 mg/ kg/ day. This finding is similar to that reported following administration to adult rats for 1 month. Preweaning rats did not therefore appear to be more susceptible than mature rats.
Crl: CD*(SD) BR immature rats, aged 15 days at the start of treatment, were dosed daily orally by gavage for 6 weeks. The rats were dosed at 0, 15, 50 and 150 mg/ kg clarithromycin, with 10 male and 10 female animals allocated to each treatment group. The control group was treated with 0.2% hydroxypropylmethylcellulose (HPMC) vehicle only.
No deaths occurred during the study. No drug-induced signs were observed. Male T3 pups had a consistently lower mean body weight than male T0 pups on the growth curves. This is considered to be a drug-related effect. Male T3 rats had lower mean food consumption than male T0 rats; male and female T2 rats appear to have consistently higher mean food consumption than male and female T0 rats (not statistically significant). The following increases in relative mean organ weights were observed: liver and kidney of male and female T3 rats, kidney of male T1 rats and spleen of female T3 rats. The increases in liver and kidney relative weights of male and female T3 rats were considered to be drug induced, but no concurrent drug-related micropathology was observed.
Renal hydronephrosis occurred in 1 female T2 rat, which was not considered to be drug-related. A small number of microscopic alterations was distributed randomly through control and treatment groups. None were drug-related.
The "no-toxic effect" level was considered to be 50 mg/ kg/ day. This finding is similar to administration of clarithromycin to adult rats for 1 month. Immature rats did not, therefore, appear to be more susceptible to clarithromycin than mature rats.
Crl:CD*(SD)BR juvenile rats, 16 days old at the start of treatment, were dosed by oral gavage for 42 to 44 treatment days (Table 34).
| Table 34 - Subchronic Toxicity Study with Clarithromycin Granules Administered Orally to Crl:CD*(SD)BR Juvenile Rats (42 to 44 treatment days) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Treatment Group | Test Material | Dosagesa (mg/ kg/ day) | Concentrationb(m g/ mL) | No/ Group | |||||||||||
| M | F | ||||||||||||||
| T0 | Vehiclec | 0 | 0 | 10 | 10 | ||||||||||
| T1 | Clarithromycin Granule for Suspension | 15 | 2.44 | 10 | 10 | ||||||||||
| T2 | Clarithromycin Granule for Suspension | 50 | 8.13 | 10 | 10 | ||||||||||
| T3 | Clarithromycin Granule for Suspension | 150 | 24.4 | 10 | 10 | ||||||||||
| |||||||||||||||
There were no deaths in the study. Excessive salivation occurred in some T3 rats (1 to 2 hours after dosing) during the last 3 weeks of treatment. Male and female pups given 150 mg/ kg/ day (T3) consistently had lower mean body weights than controls throughout the treatment period. The differences were statistically significant during the first 3 weeks of treatment. The mean weight gains from days 0 to 40 for T3 males and females were 9.4 and 6.9% less than those of T0 males and females, respectively. There were no significant differences between control and drug-treatment groups in food consumption. There were no treatment-related ophthalmic effects.
No meaningful differences were found in urinalyses and hematology parameters for the drug- treated and control rats.
There was a statistically significant decrease in the mean albumin values of T3 male and female rats when compared to controls and a statistically significant increase in the mean relative liver weights for T3 rats when compared to controls. No treatment-related gross or microscopic observations were found. A dosage of 150 mg/kg/day produced slight toxicity in the treated rats. Therefore the no-effect dosage was judged to be 50 mg/kg/day.
Wistar rats, 4 days old at the start of treatment, were dosed by oral gavage for 28 treatment days followed by a 28-day recovery period (Table 35).
| Table 35 - Subchronic Toxicity Study with Clarithromycin Granules Administered Orally to Wistar Rats (28 treatment days) | ||||
|---|---|---|---|---|
| Treatment Group | Test Material | Dosagesa (mg/ kg/ day) | No/ Group | |
| M | M | |||
| T0 | Vehicleb | 0 | 20 | 20 |
| T1 | Clarithromycin | 12.5 | 12 | 12 |
| T2 | Clarithromycin | 50 | 20 | 20 |
| T3 | Clarithromycin | 200 | 20 | 20 |
| ||||
No deaths or abnormalities in the general condition of the animals occurred during the administration or recovery periods in all treated groups.
Body weight gain was suppressed in males and females of the 200 mg/kg group from the 4th day of administration, but normal body weight gain was restored by the discontinuation of the administration. Urinalysis showed slight elevation in pH of the groups administered 50 mg/ kg or more clarithromycin, but it was normalized after discontinuation of the administration.
Hematological examinations showed a reduction in haematocrit and a reduction in hemoglobin in both sexes, a reduction in MCHC in males, and a reduction in MCH in females of the 200 mg/ kg group. Platelets were reduced in males of the 200 mg/ kg group and females of all dosing groups, and white blood cells were reduced in both sexes of the 200 mg/ kg group. These changes, however, were reversed or reduced by discontinuation of the administration.
Serum biochemical analyses revealed reduction in AST, ALP, total protein, and albumin in both sexes, a reduction in the calcium level in males, and an elevation in the blood glucose level and reduction in the creatinine level in females of the 200 mg/ kg group. These changes, however, could be reversed by discontinuation of the administration.
Necropsy revealed no abnormalities in any of the groups. Concerning organ weights, the absolute and relative weights of the thymus were reduced in males and females of the 200 mg/kg group, but normal weights were restored by discontinuation of the administration.
Changes considered to be related to suppression of body weight gains were observed in the brain, lungs, heart (males only), liver, spleen, kidneys, caecum, and testes (males only) in both sexes of the 200 mg/ kg/group. The weight of these organs recovered after discontinuation of the administration. Histopathological studies showed no changes considered to be related to the administration of clarithromycin.
Dogs
Clarithromycin was administered to juvenile beagles by oral catheter daily for 4 weeks at doses of 0 (Control), 30, 100 and 300 mg/ kg, followed by a 4-week withdrawal period to evaluate recovery. At the start of the study the beagles were 3 weeks old; each group consisted of 3 males and 3 females; and 1 female and male were added to the control and high-dose groups for the recovery study.
None of the animals died during the administration or recovery period, and no changes in the general condition of the animals were observed.
No changes considered to be due to the administration of clarithromycin were observed in the food consumption, body weight, or the results of ophthalmological, hematological, or serum biochemical examinations. Urinalysis indicated very slight occult blood in 1 female of the high-dose (300 mg/kg) group at the end of the administration period, but it was considered to be unrelated to the administration.
Pathological examinations showed dose-associated reductions in the relative weight of the kidneys in females, but these changes were considered to be unrelated to the administration because individual values were not abnormal. Necropsy revealed no abnormalities. During histological examination, fatty deposition of centrilobular hepatocytes and cell infiltration of portal areas was observed by the light microscopy, and an increase in hepatocellular fat droplets was noted by electron microscopy in the 300 mg / kg group.
In this group, also, increased fat deposition was noted relatively frequently in the kidneys. Other findings, which were considered to be unrelated to the administration, included congestion and megakaryocytic proliferation in the spleen, regional atelectasis and localised lesions of pneumonia in the lungs, leukocytic infiltration around the intrapulmonary bronchi, microfollicular formation of the thyroid glands and reduced stainability (degeneration) of Purkinje cells.
From these findings, the no-effect dose of clarithromycin in a 4-week subacute oral toxicity and a 4-week recovery study in juvenile beagles was considered to be 100 mg / kg for both males and females. The toxic dose was considered to be above 300 mg /kg.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. BIAXIN BID® (Clarithromycin Tablets, 250 mg & 500 mg) and BIAXIN® (Clarithromycin for Oral Suspension, 125 mg / 5 mL & 250 mg / 5 mL), submission control 288756, Product Monograph, BGP Pharma ULC. (DEC 17, 2024)