


Product Monograph - Stramucin
1 INDICATIONS
| STRAMUCINTM (Mupirocin Cream USP 2% w/w as mupirocin calcium) is indicated topically | ||
| for the treatment of secondarily infected traumatic lesions such as small lacerations, sutured | ||
| wounds or abrasions. | ||
| To reduce the development of drug-resistant bacteria and maintain the effectiveness of | ||
| mupirocin cream and other antibacterial drugs, mupirocin cream should be used only to treat | ||
| infections that are proven or strongly suspected to be caused by susceptible bacteria. When | ||
| culture and susceptibility information are available, they should be considered in selecting or | ||
| modifying antibacterial therapy. In the absence of such data, local epidemiology and | ||
| susceptibility patterns may contribute to the empiric selection of therapy. |
1.1 Pediatrics
Pediatrics (18 months – 16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of mupirocin 2% cream in pediatric patients have been established; therefore, Health Canada has authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): No overall difference in the efficacy or safety of mupirocin 2% cream was observed in this patient population when compared with that observed in younger patients.
2 CONTRAINDICATIONS
STRAMUCINTM is contraindicated in patients with known hypersensitivity to mupirocin or any of the excipients of mupirocin cream (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
STRAMUCINTM is not suitable for ophthalmic or intranasal use. Care should be taken to avoid contact with the eyes.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
For Topical Use Only
4.2 Recommended Dose and Dosage Adjustment
| Apply a small amount of STRAMUCINTM, with a cotton swab or gauze pad, to the affected | ||
| area 3 times daily for up 10 days. | ||
| Discontinue use and consult a physician if condition worsens or if irritation occurs. Scabs do | ||
| not have to be removed. The treated area may be covered by a dressing. Wash your hands | ||
| before and after applying. | ||
| No dosage adjustment is necessary for: | ||
| ||
| ||
| Do not mix with other preparations as there is a potential risk of dilution, resulting in a | ||
| reduction in the antibacterial activity and potential loss of stability of the mupirocin in the | ||
| cream. |
4.3 Missed Dose
If an application of STRAMUCINTM is missed, apply as soon as you remember or when it is convenient.
5 OVERDOSAGE
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Topical | Cream: 2% w/w mupirocin (as mupirocin calcium) in 15-gram and 30-gram tubes | benzyl alcohol, glycerol monostearate, mineral oil, phenoxyethanol, polyoxyl 20 cetostearyl ether, purified water and xanthan gum. |
7 WARNINGS AND PRECAUTIONS
Please see the Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information.
General
In the rare event of a possible sensitization reaction or severe local irritation occurring with the use of the product, treatment should be discontinued, the product should be wiped off and appropriate alternative therapy for the infection instituted. As with other antibacterial products, prolonged use may result in overgrowth of non-susceptible organisms.
Avoid contact with the eyes.
Prescribing mupirocin cream in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Ear/Nose/Throat
STRAMUCINTM is not suitable for intranasal use.
Gastrointestinal
Pseudomembranous colitis has been reported with the use of antibiotics and may range in severity from mild to life-threatening. Therefore, it is important to consider its diagnosis in patients who develop diarrhea during or after antibiotic use. Although this is less likely to occur with topically applied mupirocin, if prolonged or significant diarrhea occurs or the patient experiences abdominal cramps, treatment should be discontinued immediately and the patient investigated further.
Ophthalmologic
STRAMUCINTM is not suitable for ophthalmic use. Avoid contact with the eyes. If contaminated, the eyes should be thoroughly irrigated with water until the cream residue has been removed.
Sensitivity/Resistance
The use of this product may result in overgrowth of non-susceptible organisms. Also the use of this product may result in localized site irritation. Please see General Warning section above for further information or PART II MICROBIOLOGY for further information.
Sexual Health
Reproduction
There are no data on the effects of mupirocin on human fertility. Studies in rats showed no effects on fertility (see PART II TOXICOLOGY).
Skin
In the rare event of a possible sensitization reaction or severe local irritation occurring with the use of the product, treatment should be discontinued, the product should be wiped off and appropriate alternative therapy of the infection instituted.
As with other topical antibacterial products, prolonged use may result in overgrowth of non-susceptible organisms.
7.1 Special Populations
7.1.1 Pregnant Women
| The safety of STRAMUCINTM in the treatment of infections during pregnancy has not been | ||
| established. If administration to pregnant patients is considered necessary, its potential | ||
| benefits should be weighed against the possible hazards to the fetus. |
7.1.2 Breast-feeding
Caution should be exercised when STRAMUCINTM is administered to nursing mothers. If a cracked nipple is to be treated, lactation from the affected breast should be maintained by manual expression until the end of treatment. During this time, milk from the affected breast should be discarded.
7.1.3 Pediatrics
Pediatrics (18 months to 16 years): The safety and effectiveness of mupirocin cream have been established in the age-groups 18 months to 16 years [see ADVERSE REACTIONS].
7.1.4 Geriatrics
In 2 adequate and well-controlled trials, 30 subjects older than 65 years were treated with other formulations of mupirocin cream. No overall difference in the efficacy or safety of mupirocin cream was observed in this patient population when compared with that observed in younger patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
| The following local adverse reactions have been reported during therapy with mupirocin | ||
| cream: itching, burning, erythema, stinging, and dryness. It was usually not necessary to | ||
| discontinue therapy due to these adverse reactions. Systemic allergic reactions have been | ||
| reported with mupirocin cream. Cutaneous sensitization reactions to mupirocin or the cream | ||
| base have been reported rarely. |
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In previously conducted clinical studies with other formulations of mupirocin cream, the following adverse reactions were reported in connection with the use of mupirocin cream: headache, rash, and nausea.
Other adverse reactions reported rarely included: abdominal pain, burning at application site, cellulitis, dermatitis, dizziness, pruritus, secondary wound infection, and ulcerative stomatitis.
In a multi-center, double-blind, randomized, parallel-group, vehicle-controlled study in patients 18 months of age or older with secondarily infected traumatic skin lesions the safety and efficacy of STRAMUCINTM was compared against a vehicle cream. The most frequently occurring treatment emergent adverse events (TEAEs) were nasopharyngitis (2.7% Test, 1.8% Vehicle) and headache (2.7% Test, 1.4% Vehicle) in the Test group, and pyrexia in the Vehicle group (0% Test, 2.7% Vehicle). The only TEAEs that were considered possibly, probably, or definitely related to study medication were application site pruritus and worsening of ingrowing toenail in the Test group and hypersensitivity and wound complication in the Vehicle group, which occurred in only 1 subject each. Two subjects in the Vehicle group discontinued due to an adverse event.
8.3 Clinical Trial Adverse Reactions (Pediatrics)
In a clinical trial with mupirocin cream, the most frequently reported adverse experiences in the pediatric population, irrespective of relationship to drug (158 patients were treated with mupirocin cream while 152 patients received topical placebo) were nasopharyngitis (3.8%) and headache (2.5%) for topical mupirocin cream, and pyrexia (3.9%), nasopharyngitis (2.0%), cough (1.3%) and upper respiratory infection (1.3%) for topical placebo.
8.4 Post-Market Adverse Reactions
Very rare adverse events consisting of systemic allergic reactions, including anaphylaxis, urticaria, angioedema, and generalized rash have been reported in patients treated with formulations of mupirocin.
9 DRUG INTERACTIONS
9.1 Overview
No drug interactions with mupirocin cream have been identified.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Mupirocin inhibits bacterial protein synthesis by reversibly and specifically binding to bacterial isoleucyltransfer RNA (tRNA) synthetase.
Mupirocin is bactericidal at concentrations achieved by topical administration. Mupirocin is highly protein bound (greater than 97%) and the effect of wound secretions on the minimum inhibitory concentrations (MICs) of mupirocin has not been determined.
10.2 Pharmacodynamics
Mupirocin is a topical antibacterial agent showing in vivo activity against Staphylococcus aureus (including methicillin-resistant strains), S. epidermidis and beta-hemolytic Streptococcus species.
The in vitro spectrum of activity includes the following bacteria:
Commonly Susceptible Species:
- Staphylococcus aureus1,2
- Staphylococcus epidermidis1,2
- Coagulase-negative staphylococci1,2
- Streptococcus species1
- Haemophilus influenzae
- Neisseria gonorrhoeae
- Neisseria meningitidis
- Moraxella catarrhalis
- Pasteurella multocida
1Clinical efficacy has been demonstrated for susceptible isolates in approved clinical indications.
2Including beta-lactamase producing strains and methicillin-resistant strains
Resistant Species:
- Corynebacterium species
- Enterobacteriaceae
- Gram negative non-fermenting rods
- Micrococcus species
- Anaerobes
Mupirocin susceptibility (MIC) breakpoints for Staphylococcus spp.
Susceptible: Less than or equal to 1 microgram/mL
Intermediate: 2 to 256 micrograms/mL
Resistant: greater than 256 micrograms/mL
10.3 Pharmacokinetics
Absorption:
Systemic absorption of mupirocin through intact human skin is minimal. The systemic absorption of mupirocin was studied following application of mupirocin cream 3 times daily for 5 days to various skin lesions greater than 10 cm in length or 100 cm2 in area in 16 adults (aged 29 to 60 years) and 10 children (aged 3 to 12 years). Some systemic absorption was observed as evidenced by the detection of the metabolite, monic acid, in urine. Data from this trial indicated more frequent occurrence of percutaneous absorption in children (90% of subjects) compared with adults (44% of subjects); however, the observed urinary concentrations in children (0.07 to 1.3 mcg per mL [1 pediatric subject had no detectable level]) are within the observed range (0.08 to 10.03 mcg per mL [9 adults had no detectable level]) in the adult population. In general, the degree of percutaneous absorption following multiple dosing appears to be minimal in adults and children.
The effect of the concurrent application of mupirocin cream with other topical products has not been studied [see Drug Interactions].
Distribution:
No data is available.
Metabolism:
Mupirocin is suitable only for topical application. Following intravenous or oral administration, mupirocin is rapidly metabolized. The principal metabolite, monic acid, demonstrates no antibacterial activity.
Elimination:
| Mupirocin is rapidly eliminated from the body by metabolism to its inactive metabolite monic | ||
| acid which is rapidly excreted by the kidney. |
Special Populations and Conditions:
No data available.
11 STORAGE, STABILITY AND DISPOSAL
STRAMUCINTM is supplied in 15-gram and 30-gram tubes.
Store between 15ºC and 25ºC. Do not freeze.
PART II: SCIENTIFIC INFORMATION
12 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Mupirocin calcium dihydrate
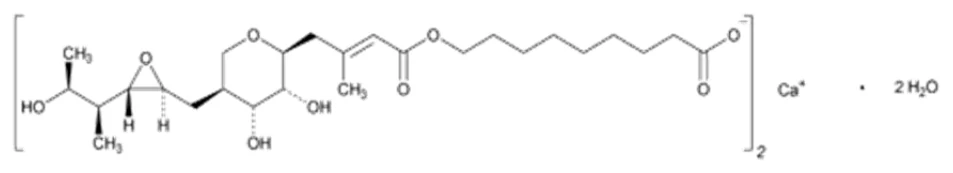
Chemical name: (αE,2S,3R,4R,5S)-5-[(2S,3S,4S,5S)-2,3-epoxy-5-hydroxy-4-methylhexyl]tetrahydro-3,4dihydroxy-β-methyl-2H-pyran-2-crotonic acid, ester with 9-hydroxynonanoic acid, calcium salt (2:1), dihydrate
Molecular formula: C52H86O18Ca ˖ 2H2O
Molecular mass: 1075.3
Structural formula:
Physicochemical properties: Mupirocin calcium is a white to almost white powder.
13 CLINICAL TRIALS
A multi-center, double-blind, randomized, parallel-group, vehicle-controlled study was conducted to compare the safety and efficacy of STRAMUCINTM against a vehicle cream in the treatment of secondarily infected traumatic skin lesions (e.g., small lacerations, sutured wounds and abrasions).
Table 2- Summary of Patient Demographics for Clinical Trials in Secondarily Infected Traumatic Skin Lesions
Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (y) | Sex M / F |
| GLK 605 | multi-center, double-blind, randomized, vehicle- controlled, parallel-group |
| 220 219 | 13.5 ± 13.3 12.4 ± 13.2 | 56% / 44% 55% / 45% |
The baseline culture results and clinical signs and symptoms were similar for both treatment groups. The primary efficacy variable was the clinical response as determined at Visit 4/Follow-up (7 days post-treatment). Clinical response was measured using the 4-point the Skin Infection Rating Scale (SIRS) scores for signs and symptoms of infection (exudate/pus, crusting, erythema/inflammation, tissue warmth, and edema scored by the investigator and pain and itching scored by the subject) and bacterial response was based on bacteriologic cultures.
Table 3- Primary Efficacy Analysis: n(%) of Clinical Success at Visit 4/Follow-up
| Analysis Population Statistics | Test | Vehicle | P-valuea |
| Per-protocol (PP), N | 175 | 165 | |
| n (%) Clinical Success | 158 (90.3%) | 117 (70.9%) | < 0.001 |
| Modified intent-to-treat (mITT), N | 181 | 176 | |
| n (%) Clinical Success | 164 (90.6%) | 124 (70.5%) | < 0.001 |
a P-values for treatment comparison from Cochran-Mantel-Haenszel (CMH) test for general association stratified by site. b Clinical Success was defined as achieving complete resolution (SIRS scores of 0) or sustained improvement (SIRS scores of 0 for exudate/pus, crusting, tissue warmth, edema and pain; and 0 or 1 for erythema/inflammation and itching) of signs and symptoms of infection. No additional antibiotic therapy required after End of Treatment. | |||
Results demonstrated that STRAMUCINTM is superior to the vehicle in achieving complete resolution or sustained improvement of the signs and symptoms of infection (p < 0.001). Bacterial eradication rates of pathogenic organisms at follow-up were also significantly greater after treatment with STRAMUCINTM than vehicle cream (p < 0.001).
Pediatrics
There were 132 pediatric subjects aged 18 months to 16 years enrolled per protocol in the secondarily infected skin lesion trials population treated with mupirocin cream. Subjects were randomized to either 10 days of topical mupirocin cream 3 times daily or 10 days of topical placebo. Clinical efficacy at follow-up (7 days post-treatment) in the per-protocol populations was 91.7% (121 of 132) for mupirocin cream and 69.0% (87 of 126) for topical placebo (p< 0.001).
14 MICROBIOLOGY
Mupirocin is active against those micro-organisms responsible for the majority of skin infections. It is particularly active against staphylococci, including methicillin-resistant strains. It is also active against many Gram-negative bacteria as a result of the high concentrations achieved after topical administration. Most strains of Morganella morganii, Serratia marcescens and Pseudomonas aeruginosa are resistant. It is not active against most anaerobic bacteria, mycobacteria, mycoplasma, chlamydia, yeast, and fungi. The in vitro activity of mupirocin against strains of various organisms is presented in the table below.
Table 4- In Vitro Activity of Mupirocin
Laboratory Species MIC (µg/mL)
Aerobic Gram-Positive
Straphylococcus
S. epidermidis 0.5
S. haemolyticus 0.5 S. hominis 0.5
S. saprophyticus 0.12 S. aureus 0.25 Streptococcus
S. pyogenes 0.12
S. species GROUP G 0.12 S. species GROUP C 0.25 S. agalactiae 0.5 S. mutans 0.5 S. sanguis 1.0 S. faecium 32 S. faecalis 64 Corynebacterium
C. hofmannii 64
C. xerosis >128 C. group >128 Bacillus subtillis 0.12 Micrococcus luteus >128
Aerobic Gram-Negative Neisseria N. meningitidis 0.02
N. gonorrhoeae 0.05 Haemophilus influenzae 0.12 Pasteurella multocida 0.25 Branhamella catarrhalis 0.2 Proteus P. vulgaris 64
P. mirabilis 128 Enterobacter E. cloacae 64
E. aerogenes 128 Escherichia coli 128 Klebsiella pneumoniae 128 Citrobacter freundii 128 Serratia marcescens 1600 Pseudomonas aeruginosa 6400 Morganella morganii 6400
Anaerobic Bacteria Peptostreptococcus anaerobius 32 Clostridium C. sporogenes 32
C. difficile 32 Propionibacterium P. acnes >128
P. granulosum >128 P. avidum >128 Peptococcus P. prevotii >128
P. asaccharolyticus >128 Bacteriodes fragilis >128
Effect of Inoculum Size:
There is only a slight effect of inoculum size on mupirocin calcium cream’s minimum inhibitory concentrations (MIC's). For Staphylococcus aureus, inocula ranging from 106 cells/mL (undiluted) to 10 cells/mL (105 dilution) resulted in a two- to four-fold variation in the MIC values.
Effect of Composition and pH of Medium:
The antibacterial activity of mupirocin was not influenced by the composition of the medium. The MIC values of mupirocin were generally two-to four-fold lower at acid pH (6.0) and two- to four-fold higher at alkaline pH (8.0) than those observed in the medium of normal pH (7.4).
Effect of Serum:
Mupirocin was highly bound to serum protein (96.5% bound) and consequently, the activity of the compound was markedly reduced in the presence of human serum.
Minimum Bactericidal Concentrations:
The MIC values of mupirocin against strains of Staphylococcus aureus ranged from 0.12 µg/mL to 2.0 µg/mL and the MBC values from 0.5 - >128 µg/mL. In most cases, the MBC values were from eight- to thirty-two-fold higher than the corresponding MIC values.
Development of Resistance:
The selection of mupirocin-resistant variants of Staphylococcus aureus after repeated exposure to increasing concentrations of the compound, occurred in a slow and stepwise fashion.
Cross-resistance to Other Antibiotics:
There is no evidence of cross-resistance between mupirocin and other antimicrobial drugs.
15 NON-CLINICAL TOXICOLOGY
Long-term studies in animals to evaluate carcinogenic potential of mupirocin calcium have not been conducted.
Results of the following studies performed with mupirocin calcium or mupirocin sodium in vitro and in vivo did not indicate a potential for genotoxicity: rat primary hepatocyte unscheduled DNA synthesis, sediment analysis for DNA strand breaks, Salmonella reversion test (Ames), Escherichia coli mutation assay, metaphase analysis of human lymphocytes, mouse lymphoma assay, and bone marrow micronuclei assay in mice.
Mupirocin administered subcutaneously to rats in this pre- and post-natal development study (dosed during late gestation through lactation) was associated with reduced offspring viability in the early postnatal period at a dose of 106.7 mg per kg, in the presence of injection site irritation and/or subcutaneous hemorrhaging. This dose is 14 times the human topical dose (approximately 60 mg mupirocin per day) based on calculations of dose divided by the entire body surface area and did not result in impaired fertility or impaired reproductive performance attributable to mupirocin. The no-observed adverse effect level in this study was 44.2 mg per kg per day, which is 6 times the human topical dose.
Developmental toxicity studies have been performed with mupirocin administered subcutaneously to rats and rabbits at doses up to 160 mg per kg per day during organogenesis. This dose is 22 and 43 times, respectively, the human topical dose (approximately 60 mg mupirocin per day) based on calculations of dose divided by the entire body surface area. Maternal toxicity was observed (body weight loss/decreased body weight gain and reduced feeding) in both species with no evidence of developmental toxicity in rats.
In rabbits, excessive maternal toxicity at the high dose precluded the evaluation of fetal outcomes. There was no developmental toxicity in rabbits at 40 mg per kg per day, 11 times the human topical dose based on calculations of dose divided by the entire body surface area.